
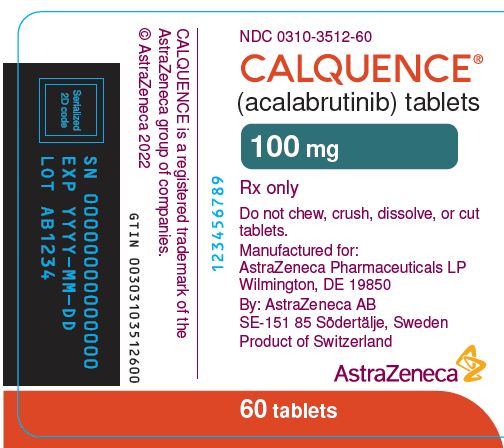
Calquence acalabrutinib 100 mg Tablet, Film Coated, 60-count — NDC 0310-3512-60 (Billing 00310-3512-60)
This is a package of 60 tablets of Calquence acalabrutinib 100 mg Tablet, Film Coated from AstraZeneca Pharmaceuticals LP, marketed since Aug 2022 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 0310-3512-60 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0310 labeler · 3512 product · 60 package
- Package marketed since
- Aug 4, 2022
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 60 EA per package
- Barcode (UPC-A, from the NDC)
- 3 0310351260 0
- Medicaid fills, this package
- 5,026 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 083668
- GCN: 52674
- GPI-14 (Medi-Span): 21532103500320
- HICL (First Databank): 048182
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 2607734
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Acalabrutinib is used to treat people with mantle cell lymphoma (MCL; a fast-growing cancer that begins in the cells of the immune system). It is also used to treat chronic lymphocytic leukemia (CLL; a type of cancer that begins in the white blood cells) and small lymphocytic lymphoma (SLL: a type of cancer that begins in the white blood cells). Acalabrutinib is in a class of medications called kinase inhibitors. It works by blocking the action of the abnormal protein that signals cancer cells to multiply. This helps stop the spread of cancer cells.
Read the full MedlinePlus article ↗- Acalabrutinib treats certain blood cancers in adults: mantle cell lymphoma, chronic lymphocytic leukemia and small lymphocytic lymphoma. For untreated mantle cell lymphoma, it is u...
- Take it by mouth about every 12 hours, with or without food. Swallow it whole with water. Don't chew or crush it, and don't open the capsules or dissolve or cut the tablets. If a d...
- Common ones are colds or other upper respiratory infections, diarrhea, headache, muscle or joint pain, fatigue, rash and bruising. Your blood counts may also drop, which is why you...
- It depends on the type. With Calquence capsules, avoid proton pump inhibitors, take the capsule 2 hours before an H2-blocker, and separate antacids by at least 2 hours. Ask me befo...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Acalabrutinib — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $261.84 | $15,710.48 / 60 tablets |
| Medicare drug plans payPart D · Q2 2026 | $260.39 | $15,623.57 / 60 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00310-3512-60 You're viewing this Main listing | 60 TABLET, FILM COATED in 1 BOTTLE | 2022-08-04 | — | Active |
| 00310-3512-95 0310-3512-95 | 60 TABLET, FILM COATED in 1 BLISTER PACK Sample | 2022-08-04 | — | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 00310-3512-95?
What NDC number is used to bill for this package of Calquence acalabrutinib 100 mg Tablet, Film Coated?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Calquence 100 mgthis 00310-3512-60 | AstraZeneca | 60 tablets | — | — | FDA listed | — |
| Calquence 100 mg 00310-4513-60 | AstraZeneca | 60 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 11166951 ↗ | Method of use | U-4426 | Aug 11, 2035 |
| US 11166951 ↗ | Method of use | U-4427 | Aug 11, 2035 |
| US 11166951 ↗ | Method of use | U-4428 | Aug 11, 2035 |
| US 11166951 ↗ | Method of use | U-4429 | Aug 11, 2035 |
| US 11166951 ↗ | Method of use | U-4430 | Aug 11, 2035 |
| US 11166951 ↗ | Method of use | U-4431 | Aug 11, 2035 |
| US 10272083 ↗ | Method of use | U-4109 | Jan 21, 2035 |
| US 11059829 ↗ | Drug substance | U-4108 | Jul 1, 2036 |
| US 9758524 ↗ | Method of use | U-4108 | Jul 11, 2032 |
| US 11059829 ↗ | Drug substance | U-2145 | Jul 1, 2036 |
| US 11059829 ↗ | Drug substance | U-2671 | Jul 1, 2036 |
| US 11059829 ↗ | Drug substance | U-2670 | Jul 1, 2036 |
| US 11059829 ↗ | Drug substance | U-2669 | Jul 1, 2036 |
| US 11059829 ↗ | Drug substance | U-2668 | Jul 1, 2036 |
| US 11059829 ↗ | Drug substance | U-2667 | Jul 1, 2036 |
| US 11059829 ↗ | Drug substance | U-2666 | Jul 1, 2036 |
| US 10272083 ↗ | Method of use | U-2519 | Jan 21, 2035 |
| US 10272083 ↗ | Method of use | U-2682 | Jan 21, 2035 |
| US 10272083 ↗ | Method of use | U-2683 | Jan 21, 2035 |
| US 10272083 ↗ | Method of use | U-2684 | Jan 21, 2035 |
| US 10272083 ↗ | Method of use | U-2685 | Jan 21, 2035 |
| US 10272083 ↗ | Method of use | U-2686 | Jan 21, 2035 |
| US 10272083 ↗ | Method of use | U-2687 | Jan 21, 2035 |
| US 11771696 ↗ | Method of use | U-3710 | Jan 21, 2035 |
| US 10239883 ↗ | Method of use | U-2666 | Jul 11, 2032 |
| US 10239883 ↗ | Method of use | U-2668 | Jul 11, 2032 |
| US 9758524 ↗ | Method of use | U-2145 | Jul 11, 2032 |
| US 7459554 ↗ | Drug substance | — | Nov 24, 2026 |
| US 9290504 ↗ | Drug substance | — | Jul 11, 2032 |
| Code | What it grants | Expires |
|---|---|---|
| D-200 | Other change requiring clinical data (3-year) | Feb 19, 2029 |
| I-960 | New indication (3-year) | Jan 16, 2028 |
Is there a generic version of CALQUENCE 100 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII D9C330MD8B
Copovidone is a synthetic polymer made by combining two types of plastic-like molecules. It acts as a binder and film-former to help hold tablet ingredients together and improve how the medicine dissolves in your body.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 2165RE0K14
A plant-based thickener made from cellulose that helps control how quickly the medicine dissolves and releases its active ingredient. It also binds ingredients together and improves the tablet's texture and handling during manufacturing.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII C9H2L21V7U
A fat derived from coconut or palm oil containing shorter fatty acid chains. It serves as a solvent and carrier to help dissolve or suspend active ingredients, improving absorption and stability in liquid formulations.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from AstraZeneca Pharmaceuticals LP labeler code 00310
- benralizumab 46.7 kg/46.7kg Liquid NDC 0310-2830-00
- anifrolumab 11.7 kg/11.7kg Solution NDC 0310-3000-10
- SAPHNELO Anifrolumab-fnia 300 mg/2mL Injection, Solution NDC 0310-3040-00
- SAPHNELO Anifrolumab-fnia 120 mg/.8mL Injection, Solution NDC 0310-3080-01
- ANDEXXA andexanet alfa 200 mg/20mL Injection, Powder, Lyophilized, For Solution NDC 0310-3200-04
- Monalizumab 50 mg/50mg Liquid NDC 0310-3333-01
- palivizumab 34.6 kg/34.6kg Liquid NDC 0310-4113-00
- Oleclumab 16.8 kg/16.8kg Liquid NDC 0310-4141-01
- IMFINZI Durvalumab 120 mg/2.4mL Injection, Solution NDC 0310-4500-12
- IMJUDO tremelimumab 25 mg/1.25mL Injection, Solution NDC 0310-4505-25
- Calquence acalabrutinib 100 mg Tablet, Film Coated NDC 0310-4513-60
- IMJUDO tremelimumab 300 mg/15mL Injection, Solution NDC 0310-4535-30
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE CALQUENCE is a kinase inhibitor indicated: • In combination with bendamustine and rituximab for the treatment of adult patients with previously untreated mantle cell lymphoma (MCL) who are ineligible for autologous hematopoietic stem cell transplantation (HSCT). (1.1 ) • For the treatment of adult patients with MCL who have received at least one prior therapy. ( 1.2 ) • For the treatment of adult patients with chronic lymphocytic leukemia (CLL) or small lymphocytic lymphoma (SLL).
( 1.3 )
1.1Previously Untreated Mantle Cell Lymphoma CALQUENCE in combination with bendamustine and rituximab is indicated for the treatment of adult patients with previously untreated mantle cell lymphoma (MCL) who are ineligible for autologous hematopoietic stem cell transplantation (HSCT).
1.2Previously Treated Mantle Cell Lymphoma CALQUENCE is indicated for the treatment of adult patients with MCL who have received at least one prior therapy.
1.3Chronic Lymphocytic Leukemia or Small Lymphocytic Lymphoma CALQUENCE is indicated for the treatment of adult patients with chronic lymphocytic leukemia (CLL) or small lymphocytic lymphoma (SLL).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Recommended dose is 100 mg orally approximately every 12 hours; swallow whole with water and with or without food. ( 2.1 ) • Advise patients not to chew, crush, dissolve, or cut tablets. ( 2.1 ) • Manage toxicities using treatment interruption, dose reduction, or discontinuation. ( 2.3 ) • Avoid CALQUENCE in patients with severe hepatic impairment. ( 8.6 )
2.1Recommended Dosage CALQUENCE Administration Instructions Advise patients to swallow tablet whole with water. Advise patients not to chew, crush, dissolve, or cut the tablets. CALQUENCE may be taken with or without food.
If a dose of CALQUENCE is missed by more than 3 hours, it should be skipped, and the next dose should be taken at its regularly scheduled time. Extra tablets of CALQUENCE should not be taken to make up for a missed dose. CALQUENCE as Monotherapy For patients with MCL, CLL or SLL, the recommended dosage of CALQUENCE is 100 mg taken orally approximately every 12 hours until disease progression or unacceptable toxicity.
CALQUENCE in Combination with Bendamustine and Rituximab For patients with previously untreated MCL, the recommended dosage of CALQUENCE is 100 mg taken orally approximately every 12 hours until disease progression or unacceptable toxicity. Start CALQUENCE on Day 1 of Cycle 1 (each cycle is 28 days) and administer until disease progression or unacceptable toxicity. Administer bendamustine 90 mg/m 2 on Days 1 and 2 and rituximab 375 mg/m 2 on Day 1 of Cycle 1 and continue for a total of 6 cycles.
Patients achieving a response (PR or CR) after the first 6 cycles may receive maintenance rituximab on Day 1 of every other cycle for a maximum of 12 additional doses, starting on Cycle 8 up to Cycle 30 [see Clinical Studies (14.1) ] . CALQUENCE in Combination with Obinutuzumab For patients with previously untreated CLL or SLL, the recommended dosage of CALQUENCE is 100 mg taken orally approximately every 12 hours until disease progression or unacceptable toxicity. Start CALQUENCE at Cycle 1 (each cycle is 28 days).
Start obinutuzumab at Cycle 2 for a total of 6 cycles and refer to the obinutuzumab prescribing information for recommended dosing. Administer CALQUENCE prior to obinutuzumab when given on the same day. CALQUENCE in Combination with Venetoclax For patients with previously untreated CLL or SLL, the recommended dosage of CALQUENCE is 100 mg taken orally approximately every 12 hours until disease progression, unacceptable toxicity or completion of 14 cycles of treatment.
Start CALQUENCE at Cycle 1 (each cycle is 28 days). Start venetoclax at Cycle 3 for total of 12 cycles. Start venetoclax at 20 mg daily for first week of treatment and increase weekly as per dosing schedule for 5-week ramp up (up to 400 mg daily) as described in the venetoclax USPI.
Refer to the venetoclax USPI for additional details.
2.2Recommended Dosage for Drug Interactions Dosage Modifications for Use with CYP3A Inhibitors or Inducers These are described in Table 1 [see Drug Interactions (7) ]. Table 1: Recommended Dosage Modifications for Use with CYP3A Inhibitors or Inducers CYP3A Co-administered Drug Recommended CALQUENCE use Inhibition Strong CYP3A inhibitor Avoid co-administration. If these inhibitors will be used short-term (such as anti‑infectives for up to seven days), interrupt CALQUENCE.
After discontinuation of strong CYP3A inhibitor for at least 24 hours, resume previous dosage of CALQUENCE. Moderate CYP3A inhibitor Reduce the CALQUENCE 100 mg every 12 hours dosage to 100 mg once daily. Induction Strong CYP3A inducer Avoid co-administration.
If co-administration is unavoidable, increase CALQUENCE dosage to 200 mg approximately every 12 hours.
2.3Dosage Modifications for Adverse Reactions Recommended dosage modifications are provided in Table 2, 3 and 4. Table 2: Recommended Dosage Modifications for Adverse Reactions in Patients Receiving CALQUENCE Monotherapy and CALQUENCE in Combination with Obinutuzumab Event Adverse Reaction… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets:100 mg acalabrutinib, orange, oval, film-coated, biconvex, debossed with ‘ACA 100’ on one side and plain on the other. Tablets: 100 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Serious and Opportunistic Infections: Monitor for signs and symptoms of infection and treat promptly. ( 5.1 ) • Hemorrhage: Monitor for bleeding and manage appropriately. ( 5.2 ) • Cytopenias: Monitor complete blood counts regularly.
( 5.3 ) • Second Primary Malignancies: Other malignancies have occurred, including skin cancers and other solid tumors. Advise patients to use sun protection. ( 5.4 ) • Cardiac Arrhythmias: Monitor for symptoms of arrhythmias and manage.
( 5.5 ) • Hepatotoxicity, Including Drug Induced Liver Injury: Monitor hepatic function throughout treatment. ( 5.6 )
5.1Serious and Opportunistic Infections Fatal and serious infections, including opportunistic infections, have occurred in patients with hematologic malignancies treated with CALQUENCE. Serious or Grade 3 or higher infections (bacterial, viral, or fungal) occurred in 29% of 2,055 patients exposed to CALQUENCE in clinical trials, most often due to respiratory tract infections (18% of all patients, including pneumonia in 14%) [see Adverse Reactions (6.1) ] . These infections predominantly occurred in the absence of Grade 3 or 4 neutropenia, with neutropenic infection reported in 8% of all patients.
Opportunistic infections in recipients of CALQUENCE have included, but are not limited to, hepatitis B virus reactivation, fungal pneumonia, Pneumocystis jirovecii pneumonia, Epstein-Barr virus reactivation, cytomegalovirus, and progressive multifocal leukoencephalopathy (PML). Consider prophylaxis in patients who are at increased risk for opportunistic infections. Monitor patients for signs and symptoms of infection and treat promptly.
In an additional cohort of patients receiving CALQUENCE in combination with venetoclax with obinutuzumab (AVO) (an unapproved regimen for previously untreated CLL/SLL in AMPLIFY), serious or Grade 3 or higher infections occurred in 25% receiving AVO compared to 14% in patients receiving AV. Fatal infections occurred in 6% receiving AVO compared to 3.1% of patients receiving AV, most commonly due to COVID-19. The safety and effectiveness of AVO has not been established in patients with previously untreated CLL/SLL [see Clinical Studies (14.3) ].
5.2Hemorrhage Fatal and serious hemorrhagic events have occurred in patients treated with CALQUENCE. Major hemorrhage (serious or Grade 3 or higher bleeding or any central nervous system bleeding) occurred in 4.7% of patients, with fatal hemorrhage occurring in 0.1% of 2,055 patients exposed to CALQUENCE in clinical trials. Bleeding events of any grade, excluding bruising and petechiae, occurred in 39% of patients [ see Adverse Reactions (6.1) ] .
Use of antithrombotic agents concomitantly with CALQUENCE may further increase the risk of hemorrhage. In clinical trials, major hemorrhage occurred in 5% of patients taking CALQUENCE without antithrombotic agents and 3.2% of patients taking CALQUENCE with antithrombotic agents. Consider the risks and benefits of antithrombotic agents when co-administered with CALQUENCE.
Monitor patients for signs of bleeding. Consider the benefit-risk of withholding CALQUENCE for 3 to 7 days pre- and post-surgery depending upon the type of surgery and the risk of bleeding.
5.3Cytopenias CALQUENCE can cause Grade 3 or 4 cytopenias. Grade 3 or 4 cytopenias included absolute neutrophil count decreased (28%), absolute lymphocyte count decreased (10%), hemoglobin decreased (9%), and platelets decreased (9%) in 1,758 patients treated with CALQUENCE alone and in combination with obinutuzumab or venetoclax; Grade 4 neutropenia developed in 14% [see Adverse Reactions (6.1) ] . Monitor complete blood counts regularly during treatment.
Interrupt treatment, reduce the dose, or discontinue treatment as warranted [see Dosage and Administration (2.3) ] .
5.4Second Primary Malignancies Second primary malignancies, including skin cancers and other solid tumors, occurred in 16% of 2,055 patients exposed to CALQUENCE in clinical trials [see A… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are discussed in greater detail in other sections of the labeling: • Serious and Opportunistic Infections [see Warnings and Precautions (5.1) ] • Hemorrhage [see Warnings and Precautions (5.2) ] • Cytopenias [see Warnings and Precautions (5.3) ] • Second Primary Malignancies [see Warnings and Precautions (5.4) ] • Cardiac Arrhythmias [see Warnings and Precautions (5.5) ] • Hepatotoxicity, including DILI [see Warnings and Precautions (5.6) ] The most common adverse reactions (≥ 30%), excluding laboratory abnormalities, are upper respiratory tract infection, diarrhea, headache, and musculoskeletal pain.
The most common Grade 3 or 4 laboratory abnormalities (≥ 10%) are absolute neutrophil count decreased, uric acid increased, absolute lymphocyte count decreased, and platelets decreased. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact AstraZeneca at 1-800-236-9933 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data in the Warnings and Precautions reflect exposure to CALQUENCE 100 mg approximately every 12 hours in 2,055 patients with hematologic malignancies. Treatment includes CALQUENCE monotherapy in 1258 patients in 9 trials, and CALQUENCE combinations in 797 patients in 4 trials.
Among these recipients of CALQUENCE, 89% were exposed for at least 6 months and 82% were exposed for at least one year. In this pooled safety population, adverse reactions in ≥ 30% of 2,055 patients, excluding laboratory abnormalities, were upper respiratory tract infection (37%), diarrhea (36%), headache (35%), and musculoskeletal pain (32%). The most common Grade 3 or 4 laboratory abnormalities (≥ 10%) were absolute neutrophil count decreased (32%), uric acid increased (27%), absolute lymphocyte count decreased (21%) and platelets decreased (10%).
Previously Untreated Mantle Cell Lymphoma The safety data described below reflect exposure to CALQUENCE (100 mg approximately every 12 hours, with or without BR) in patients with MCL [see Clinical Studies (14.1) ] . ECHO The safety of CALQUENCE in combination with bendamustine and rituximab (CALQUENCE plus BR) was evaluated in 297 patients with previously untreated MCL in ECHO [see Clinical Studies (14.1) ] . The trial enrolled patients with previously untreated MCL, ≥ 65 years of age with no intention for transplant, total bilirubin ≤ 1.5 × ULN, AST or ALT ≤ 2.5 × ULN, and estimated creatinine clearance of > 50 mL/min.
Patients received 6 cycles (as 28-day cycles) of CALQUENCE 100 mg orally twice daily (n = 297) or placebo (n = 297) in combination with bendamustine and rituximab. Patients then received CALQUENCE 100 mg orally twice daily or placebo continuously until progressive disease or unacceptable toxicity, with 12 additional dosages of rituximab every other cycle up to Cycle 30. The median duration of treatment with CALQUENCE was 28.6 months.
A total of 171 (57.6%) patients were treated with CALQUENCE for ˃ 24 months and 122 (41.1%) patients were treated for ˃ 36 months. Serious adverse reactions occurred in 69% of patients who received CALQUENCE plus BR. Serious adverse reactions reported in ≥ 2% of patients were pneumonia (23%; includes COVID-19 pneumonia), COVID-19 (20%; includes COVID-19 pneumonia), pyrexia (6%), second primary malignancy (7%), rash (3.4%), febrile neutropenia (3.4%), atrial fibrillation (3%), sepsis (2.7%), and anemia (2.4%).
Fatal adverse reactions that occurred within 30 days of the last study treatment were reported in 12% who received CALQUENCE plus BR including COVID-19 (6%; includes COVID-19 pneumonia), pneumonia (1%), sepsis (0.3%), second primary malignancy (0.7%), and pneumonitis (0.3%). Adve… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Strong CYP3A Inhibitors : Avoid co-administration with CALQUENCE. ( 2.2 , 7 ) • Moderate CYP3A Inhibitors : Reduce the dosage of CALQUENCE. ( 2.2 , 7 ) • Strong CYP3A Inducers : Avoid co-administration with CALQUENCE. If co-administration is unavoidable, increase the dosage of CALQUENCE. ( 2.2 , 7 )
7.1Effect of Other Drugs on CALQUENCE Strong CYP3A Inhibitors Clinical Effect Co-administration of CALQUENCE with a strong CYP3A inhibitor increased acalabrutinib plasma concentrations [see Clinical Pharmacology (12.3) ] . Increased acalabrutinib concentrations may result in increased toxicity. Prevention or Management Avoid co-administration of CALQUENCE with strong CYP3A inhibitors.
Alternatively, if the inhibitor will be used short-term, interrupt CALQUENCE [see Dosage and Administration (2.2) ]. Moderate CYP3A Inhibitors Clinical Effect Co-administration of CALQUENCE with a moderate CYP3A inhibitor may increase acalabrutinib plasma concentration [see Clinical Pharmacology (12.3) ] . Increased acalabrutinib concentrations may result in increased toxicity.
Prevention or Management Reduce the dosage of CALQUENCE when co-administered with a moderate CYP3A inhibitor [see Dosage and Administration (2.2) ]. Strong CYP3A Inducers Clinical Effect Co-administration of CALQUENCE with a strong CYP3A inducer decreased acalabrutinib plasma concentration [see Clinical Pharmacology (12.3) ] . Decreased acalabrutinib concentrations may reduce CALQUENCE activity.
Prevention or Management Avoid co-administration of CALQUENCE with strong CYP3A inducers. If co-administration is unavoidable, increase the dosage of CALQUENCE [see Dosage and Administration (2.2) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pregnancy: May cause fetal harm and dystocia. ( 8.1 ) • Lactation: Advise not to breastfeed. ( 8.2 ) • Severe Hepatic Impairment: Avoid use of CALQUENCE. ( 8.6 )
8.1Pregnancy Risk Summary Based on findings in animals, CALQUENCE may cause fetal harm and dystocia when administered to a pregnant woman. There are no available data in pregnant women to inform the drug-associated risk. In animal reproduction studies, administration of acalabrutinib to animals during organogenesis resulted in dystocia in rats and reduced fetal growth in rabbits at maternal exposures (AUC) 2 times exposures in patients at the recommended dose of 100 mg approximately every 12 hours ( see Data ) .
Advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data In a combined fertility and embryo-fetal development study in female rats, acalabrutinib was administered orally at doses up to 200 mg/kg/day starting 14 days prior to mating through gestational day [GD] 17. No effects on embryo-fetal development and survival were observed.
The AUC at 200 mg/kg/day in pregnant rats was approximately 9 times the AUC in patients at the recommended dose of 100 mg approximately every 12 hours. The presence of acalabrutinib and its active metabolite were confirmed in fetal rat plasma. In an embryo-fetal development study in rabbits, pregnant animals were administered acalabrutinib orally at doses up to 200 mg/kg/day during the period of organogenesis (from GD 6-18).
Administration of acalabrutinib at doses ≥ 100 mg/kg/day produced maternal toxicity and 100 mg/kg/day resulted in decreased fetal body weights and delayed skeletal ossification. The AUC at 100 mg/kg/day in pregnant rabbits was approximately 2 times the AUC in patients at 100 mg approximately every 12 hours. In a pre- and postnatal development study in rats, acalabrutinib was administered orally to pregnant animals during organogenesis, parturition and lactation, at doses of 50, 100, and 150 mg/kg/day.
Dystocia (prolonged or difficult labor) and mortality of offspring were observed at doses ≥ 100 mg/kg/day. The AUC at 100 mg/kg/day in pregnant rats was approximately 2 times the AUC in patients at 100 mg approximately every 12 hours. Underdeveloped renal papilla was also observed in F1 generation offspring at 150 mg/kg/day with an AUC approximately 5 times the AUC in patients at 100 mg approximately every 12 hours.
8.2Lactation Risk Summary No data are available regarding the presence of acalabrutinib or its active metabolite in human milk, its effects on the breastfed child, or on milk production. Acalabrutinib and its active metabolite were present in the milk of lactating rats. Due to the potential for adverse reactions in a breastfed child from CALQUENCE, advise lactating women not to breastfeed while taking CALQUENCE and for 2 weeks after the last dose.
8.3Females and Males of Reproductive Potential CALQUENCE may cause embryo-fetal harm and dystocia when administered to pregnant women [see Use in Specific Populations (8.1) ] . Pregnancy Testing Pregnancy testing is recommended for females of reproductive potential prior to initiating CALQUENCE therapy. Contraception Females Advise female patients of reproductive potential to use effective contraception during treatment with CALQUENCE and for 1 week following the last dose of CALQUENCE.
If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be informed of the potential hazard to a fetus.
8.4Pediatric Use The safety and efficacy of CALQUENCE in pediatric patients have not been esta… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings in animals, CALQUENCE may cause fetal harm and dystocia when administered to a pregnant woman. There are no available data in pregnant women to inform the drug-associated risk. In animal reproduction studies, administration of acalabrutinib to animals during organogenesis resulted in dystocia in rats and reduced fetal growth in rabbits at maternal exposures (AUC) 2 times exposures in patients at the recommended dose of 100 mg approximately every 12 hours ( see Data ) .
Advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data In a combined fertility and embryo-fetal development study in female rats, acalabrutinib was administered orally at doses up to 200 mg/kg/day starting 14 days prior to mating through gestational day [GD] 17. No effects on embryo-fetal development and survival were observed.
The AUC at 200 mg/kg/day in pregnant rats was approximately 9 times the AUC in patients at the recommended dose of 100 mg approximately every 12 hours. The presence of acalabrutinib and its active metabolite were confirmed in fetal rat plasma. In an embryo-fetal development study in rabbits, pregnant animals were administered acalabrutinib orally at doses up to 200 mg/kg/day during the period of organogenesis (from GD 6-18).
Administration of acalabrutinib at doses ≥ 100 mg/kg/day produced maternal toxicity and 100 mg/kg/day resulted in decreased fetal body weights and delayed skeletal ossification. The AUC at 100 mg/kg/day in pregnant rabbits was approximately 2 times the AUC in patients at 100 mg approximately every 12 hours. In a pre- and postnatal development study in rats, acalabrutinib was administered orally to pregnant animals during organogenesis, parturition and lactation, at doses of 50, 100, and 150 mg/kg/day.
Dystocia (prolonged or difficult labor) and mortality of offspring were observed at doses ≥ 100 mg/kg/day. The AUC at 100 mg/kg/day in pregnant rats was approximately 2 times the AUC in patients at 100 mg approximately every 12 hours. Underdeveloped renal papilla was also observed in F1 generation offspring at 150 mg/kg/day with an AUC approximately 5 times the AUC in patients at 100 mg approximately every 12 hours.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and efficacy of CALQUENCE in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use CLL and Previously Treated MCL Of the 1,758 CALQUENCE-treated patients with B-cell malignancies (excluding previously untreated MCL) in clinical trials, 1,074 (61%) were 65 years of age or older, and 341 (19%) were 75 years of age or older. Among patients 65 years of age or older, 73% had Grade 3 or higher adverse reactions and 55% had serious adverse reactions. Among patients younger than age 65, 58% had Grade 3 or higher adverse reactions and 35% had serious adverse reactions.
No clinically relevant differences in efficacy were observed between patients ≥ 65 years and younger. Of patients that received CALQUENCE in combination with venetoclax in AMPLIFY, 33% (97/291) were ≥ 65 years of age, and 4.5% (13/291) were ≥ 75 years of age. In patients 65 years of age or older and younger than age 65, the fatal adverse reactions were 5% and 2.6% respectively.
No clinically relevant differences in efficacy were observed between patients ≥ 65 years of age and younger adults. Previously Untreated MCL Of the 297 CALQUENCE-treated patients with previously untreated MCL, 214 (72%) were 65 to 74 years of age and 83 (28%) were 75 years of age and older. No clinically relevant differences in safety or efficacy were observed between patients ages 65 to 74 years and those who were 75 years of age and older.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Acalabrutinib is a small-molecule inhibitor of Bruton tyrosine kinase (BTK). Acalabrutinib and its active metabolite, ACP-5862, form a covalent bond with a cysteine residue in the BTK active site, leading to inhibition of BTK enzymatic activity. BTK is a signaling molecule of the B cell antigen receptor (BCR) and cytokine receptor pathways.
In B cells, BTK signaling results in activation of pathways necessary for B-cell proliferation, trafficking, chemotaxis, and adhesion. In nonclinical studies, acalabrutinib inhibited BTK‑mediated activation of downstream signaling proteins CD86 and CD69 and inhibited malignant B-cell proliferation and tumor growth in mouse xenograft models.
12.2Pharmacodynamics In patients with B-cell malignancies dosed with acalabrutinib 100 mg approximately every 12 hours, median steady state BTK occupancy of ≥ 95% in peripheral blood was maintained over 12 hours, resulting in inactivation of BTK throughout the recommended dosing interval. Cardiac Electrophysiology At a dose 4 times the approved recommended dosage, CALQUENCE does not prolong the QTc interval to any clinically relevant extent.
12.3Pharmacokinetics Acalabrutinib and its active metabolite, ACP-5862, exposures increase proportionally with dose across a dose range of 75 to 250 mg (0.75 to 2.5 times the approved recommended single dosage) in patients with B-cell malignancies. At the recommended dose of 100 mg twice daily, the geometric mean (% coefficient of variation [CV]) daily area under the plasma drug concentration over time curve (AUC 24h ) and maximum plasma concentration (C max ) for acalabrutinib were 1843 (38%) ng•h/mL and 563 (29%) ng/mL, respectively, and for ACP-5862 were 3947 (43%) ng•h/mL and 451 (52%) ng/mL, respectively.
Absorption The geometric mean absolute bioavailability of acalabrutinib was 25%. Median (min, max) time to peak plasma concentration (T max ) of acalabrutinib and its active metabolite, ACP-5862 were 0.5 (0.2, 3.0) hours and 0.75 (0.5, 4.0) hours, respectively. Effect of Food In healthy subjects, administration of a single 100 mg dose of acalabrutinib with a high-fat, high-calorie meal (approximately 918 calories, 59 grams carbohydrate, 59 grams fat, and 39 grams protein) did not affect the mean AUC as compared to dosing under fasted conditions.
Resulting C max decreased by 54% and T max was delayed 1-2 hours. Distribution The geometric mean (% CV) steady-state volume of distribution (V ss ) of acalabrutinib and its active metabolite, ACP-5862 was approximately 101 (52%) L and 67 (32%) L, respectively. Reversible binding to human plasma protein of acalabrutinib and its active metabolite, ACP-5862, were 97.5% and 98.6%, respectively.
The mean blood-to-plasma ratio of acalabrutinib and its active metabolite, ACP-5862, was 0.8 and 0.7, respectively. Elimination The geometric mean (% CV) terminal elimination half-life (t 1/2 ) of acalabrutinib and its active metabolite, ACP-5862, were 1.4 (50%) hours and 6.4 (37%) hours, respectively. The geometric mean (%CV) apparent oral clearance (CL/F) of acalabrutinib and its active metabolite, ACP-5862, were 148 (33%) L/hr and 19 (23%) L/hr, respectively.
Metabolism Acalabrutinib is predominantly metabolized by CYP3A enzymes, and to a minor extent, by glutathione conjugation and amide hydrolysis, based on in vitro studies. ACP-5862 was identified as the major active metabolite in plasma with a geometric mean exposure (AUC) that was approximately 2- to 3-fold higher than the exposure of acalabrutinib. ACP-5862 is approximately 50% less potent than acalabrutinib with regard to BTK inhibition.
Excretion Following administration of a single 100 mg radiolabeled acalabrutinib dose in healthy subjects, 84% of the dose was recovered in the feces (< 2% unchanged) and 12% of the dose was recovered in the urine (< 2% unchanged). Specific Populations There were no clinically significant differences in the pharmacokinetics of acalabrutin… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Acalabrutinib is a small-molecule inhibitor of Bruton tyrosine kinase (BTK). Acalabrutinib and its active metabolite, ACP-5862, form a covalent bond with a cysteine residue in the BTK active site, leading to inhibition of BTK enzymatic activity. BTK is a signaling molecule of the B cell antigen receptor (BCR) and cytokine receptor pathways.
In B cells, BTK signaling results in activation of pathways necessary for B-cell proliferation, trafficking, chemotaxis, and adhesion. In nonclinical studies, acalabrutinib inhibited BTK‑mediated activation of downstream signaling proteins CD86 and CD69 and inhibited malignant B-cell proliferation and tumor growth in mouse xenograft models.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied Pack Size Contents NDC Number 60-count bottle Bottle containing 60 tablets with a child-resistant closure 100 mg, orange, oval, biconvex tablet, with debossment ‘ACA100’ on one side and plain on the reverse 0310-3512-60 Storage Store at 20°C-25°C (68°F-77°F); excursions permitted to 15°C-30°C (59°F-86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION CALQUENCE (acalabrutinib) is a kinase inhibitor. The molecular formula for acalabrutinib maleate is C 26 H 23 N 7 O 2 •C 4 H 4 O 4 .H 2 O, and the molecular weight is 599.59. The chemical name is 4-{8-Amino-3-[(2 S )-1-(but-2-ynoyl) pyrrolidin-2-yl] imidazo[1,5- a ]pyrazin-1-yl}- N -(pyridin-2-yl)benzamide (2 Z )-2-butenedioic acid hydrate.
The chemical structure of acalabrutinib is shown below: Acalabrutinib maleate is a white to pale brown powder with pH-dependent solubility. It is freely soluble in water at pH values below 3 and practically insoluble at pH values above 6. CALQUENCE tablets are for oral administration.
Each tablet contains 100 mg of acalabrutinib (equivalent to 129 mg of acalabrutinib maleate). Inactive ingredients in the tablet core are low-substituted hydroxypropyl cellulose, mannitol, microcrystalline cellulose, and sodium stearyl fumarate. The tablet coating consists of copovidone, ferric oxide yellow, ferric oxide red, hypromellose, medium-chain triglycerides, polyethylene glycol 3350, purified water, and titanium dioxide. chemical_structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Serious and Opportunistic Infections Inform patients of the possibility of serious infection and to immediately report signs or symptoms suggestive of infection [see Warnings and Precautions (5.1) ] . Hemorrhage Inform patients to immediately report signs or symptoms of bleeding.
Inform patients that CALQUENCE may need to be interrupted for major surgeries [see Warnings and Precautions (5.2) ] . Cytopenias Inform patients that they will need periodic blood tests to check blood counts during treatment with CALQUENCE [see Warnings and Precautions (5.3) ] . Second Primary Malignancies Inform patients that other malignancies have been reported in patients who have been treated with CALQUENCE, including skin cancer and other solid tumors.
Advise patients to use sun protection [see Warnings and Precautions (5.4) ] . Cardiac Arrhythmias Counsel patients to immediately report any signs of palpitations, dizziness, fainting, chest discomfort, and shortness of breath [see Warnings and Precautions (5.5) ] . Hepatotoxicity, Including Drug-Induced Liver Injury: Inform patients that liver problems, including drug-induced liver injury and abnormalities in liver tests, may develop during CALQUENCE treatment.
Advise patients to contact their healthcare provider immediately if they experience abdominal discomfort, dark urine, or jaundice [see Warnings and Precautions (5.6) ]. Pregnancy Complication CALQUENCE may cause fetal harm and dystocia. Advise women to use effective contraception during treatment and for 1 week after the last dose of CALQUENCE [see Use in Specific Populations (8.3) ] .
Lactation Advise females not to breastfeed during treatment with CALQUENCE and for 2 weeks after the last dose [see Use in Specific Populations (8.2) ] . Dosing Instructions Instruct patients to take CALQUENCE orally twice daily, about 12 hours apart. CALQUENCE may be taken with or without food.
Advise patients that CALQUENCE tablets should be swallowed whole with a glass of water, without chewing, crushing, dissolving, or cutting [see Dosage and Administration (2.1) ] . Missed Dose Advise patients that if they miss a dose of CALQUENCE, they may still take it up to 3 hours after the time they would normally take it. If more than 3 hours have elapsed, they should be instructed to skip that dose and take their next dose of CALQUENCE at the usual time.
Warn patients they should not take extra tablets to make up for the dose that they missed [see Dosage and Administration (2.1) ] . Drug Interactions Advise patients to inform their healthcare providers of all concomitant medications, including over‑the‑counter medications, vitamins and herbal products [see Drug Interactions (7) ] . Distributed by: AstraZeneca Pharmaceuticals LP Wilmington, DE 19850 CALQUENCE is a registered trademark of the AstraZeneca group of companies. ©AstraZeneca 2026
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Acalabrutinib and its active metabolite, ACP-5862, exposures increase proportionally with dose across a dose range of 75 to 250 mg (0.75 to 2.5 times the approved recommended single dosage) in patients with B-cell malignancies. At the recommended dose of 100 mg twice daily, the geometric mean (% coefficient of variation [CV]) daily area under the plasma drug concentration over time curve (AUC 24h ) and maximum plasma concentration (C max ) for acalabrutinib were 1843 (38%) ng•h/mL and 563 (29%) ng/mL, respectively, and for ACP-5862 were 3947 (43%) ng•h/mL and 451 (52%) ng/mL, respectively.
Absorption The geometric mean absolute bioavailability of acalabrutinib was 25%. Median (min, max) time to peak plasma concentration (T max ) of acalabrutinib and its active metabolite, ACP-5862 were 0.5 (0.2, 3.0) hours and 0.75 (0.5, 4.0) hours, respectively. Effect of Food In healthy subjects, administration of a single 100 mg dose of acalabrutinib with a high-fat, high-calorie meal (approximately 918 calories, 59 grams carbohydrate, 59 grams fat, and 39 grams protein) did not affect the mean AUC as compared to dosing under fasted conditions.
Resulting C max decreased by 54% and T max was delayed 1-2 hours. Distribution The geometric mean (% CV) steady-state volume of distribution (V ss ) of acalabrutinib and its active metabolite, ACP-5862 was approximately 101 (52%) L and 67 (32%) L, respectively. Reversible binding to human plasma protein of acalabrutinib and its active metabolite, ACP-5862, were 97.5% and 98.6%, respectively.
The mean blood-to-plasma ratio of acalabrutinib and its active metabolite, ACP-5862, was 0.8 and 0.7, respectively. Elimination The geometric mean (% CV) terminal elimination half-life (t 1/2 ) of acalabrutinib and its active metabolite, ACP-5862, were 1.4 (50%) hours and 6.4 (37%) hours, respectively. The geometric mean (%CV) apparent oral clearance (CL/F) of acalabrutinib and its active metabolite, ACP-5862, were 148 (33%) L/hr and 19 (23%) L/hr, respectively.
Metabolism Acalabrutinib is predominantly metabolized by CYP3A enzymes, and to a minor extent, by glutathione conjugation and amide hydrolysis, based on in vitro studies. ACP-5862 was identified as the major active metabolite in plasma with a geometric mean exposure (AUC) that was approximately 2- to 3-fold higher than the exposure of acalabrutinib. ACP-5862 is approximately 50% less potent than acalabrutinib with regard to BTK inhibition.
Excretion Following administration of a single 100 mg radiolabeled acalabrutinib dose in healthy subjects, 84% of the dose was recovered in the feces (< 2% unchanged) and 12% of the dose was recovered in the urine (< 2% unchanged). Specific Populations There were no clinically significant differences in the pharmacokinetics of acalabrutinib and its active metabolite, ACP‑5862, based on age (32 to 90 years), sex, race (Caucasian, African American), body weight (40 to 149 kg), or mild to moderate renal impairment (estimated glomerular filtration rate [eGFR] by Modification of Diet in Renal Disease [MDRD] equation: 30 to < 90 mL/min).
The effect of severe renal impairment (eGFR < 30 mL/min, MDRD) or renal impairment requiring dialysis on the pharmacokinetics of acalabrutinib is unknown. Patients with Hepatic Impairment The AUC of acalabrutinib increased 1.9-fold in subjects with mild hepatic impairment (Child-Pugh class A), 1.5-fold in subjects with moderate hepatic impairment (Child-Pugh class B) and 5.3-fold in subjects with severe hepatic impairment (Child-Pugh class C) compared to subjects with normal liver function. No clinically relevant PK difference in ACP-5862 was observed in subjects with severe hepatic impairment (Child-Pugh Class C) compared to subjects with normal liver function. of acalabrutinib increased 1.9-fold in subjects with mild hepatic impairment (Child-Pugh class A), 1.5-fold in subjects with moderate hepatic impairment (Child-Pugh class B) and 5.3-fold in subjects with severe h… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics In patients with B-cell malignancies dosed with acalabrutinib 100 mg approximately every 12 hours, median steady state BTK occupancy of ≥ 95% in peripheral blood was maintained over 12 hours, resulting in inactivation of BTK throughout the recommended dosing interval. Cardiac Electrophysiology At a dose 4 times the approved recommended dosage, CALQUENCE does not prolong the QTc interval to any clinically relevant extent.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Previously Untreated Mantle Cell Lymphoma DOCVARIABLE vault_nd_4d1e0c80-2ff6-409f-bee7-897264eadbff \* MERGEFORMAT ECHO The efficacy of CALQUENCE in patients with previously untreated MCL was evaluated in a randomized, double blind, placebo controlled, multicenter study (ECHO; NCT02972840). The study enrolled 598 patients who were ≥ 65 years of age and who had no intention for transplant. The study excluded patients with total bilirubin > 1.5 × upper limit of normal (ULN), AST or ALT > 2.5 × ULN, or estimated creatinine clearance of ≤ 50 mL/min.
Patients were randomized in a 1:1 ratio to receive CALQUENCE plus bendamustine and rituximab (CALQUENCE plus BR) or placebo plus BR. Dosing for both arms was administered in 28-day cycles as follows: • CALQUENCE plus BR was administered for a maximum of 6 treatment cycles. CALQUENCE 100 mg orally was administered twice daily starting on Cycle 1 Day 1.
Bendamustine was administered at 90 mg/m 2 intravenously over 30 minutes on Days 1 and 2 of each of 6 cycles. Rituximab was administered at 375 mg/m 2 intravenously on Day 1 of each cycle for 6 cycles. • For patients achieving a response (PR or CR), CALQUENCE 100 mg orally twice daily was administered continuously, in combination with rituximab given at 375 mg/m 2 on Day 1 every other cycle for a maximum of 12 additional doses up to Cycle 30. After discontinuation of rituximab, patients continued CALQUENCE monotherapy at 100 mg orally twice daily until disease progression or unacceptable toxicity.
Patients on the control arm received the same regimen but placebo in lieu of CALQUENCE. Crossover to CALQUENCE monotherapy was permitted for patients in the placebo plus BR arm at disease progression. Of all patients randomized, the median age was 71 years (range: 65-86); 71% were male; 78% were White, 16% Asian, 0.5% were Black or African American.
In total, 80% had classic histology of MCL, 7.7% had blastoid MCL, and 5.5% had pleomorphic MCL. The simplified MIPI (Mantle Cell Lymphoma International Prognostic Index) score was low in 33%, intermediate in 43%, and high in 24% of patients. A total of 38% of patients had tumor bulk ≥ 5 cm and 86% had Ann Arbor stage IV disease.
The major efficacy outcome was progression-free survival (PFS) as assessed by an Independent Review Committee (IRC) using the Lugano Classification. Efficacy results are presented in Table 15. The Kaplan-Meier curves for PFS are shown in Figure 1.
At this prespecified interim analysis, the median follow-up for PFS was 49.8 months in both arms. Table 15. Efficacy Results in Patients with Previously Untreated MCL in ECHO Outcomes per IRC CALQUENCE plus BR N= 299 Placebo plus BR N= 299 Progression-Free Survival a Median (95% CI), months 66.4 (55.1, NE) 49.6 (36.0, 64.1) HR b (95% CI) 0.73 (0.57, 0.94) P-value c 0.016 Overall Response Rate (ORR) (CR + PR) ORR n (%) 272 (91) 263 (88) 95% CI 87, 94 84, 91 CR n (%) 199 (67) 160 (54) PR n (%) 73 (24) 103 (34) p-value 0.220 HR = hazard ratio, CR = complete response, PR = partial response, NE – not evaluable a Stratified by randomization stratification factors: Geographic Regions (North American, Western Europe, Other) and simplified MIPI Score (Low risk [0 to 3], Intermediate risk [4 to 5], High Risk [6 to 11]). b Estimated based on stratified Cox Proportional Hazards model for hazard ratio (95% CI). c Estimated based on stratified log-rank test for p-value, with an alpha level of 0.039 derived by the O’Brien-Fleming method.
Figure 1. Kaplan-Meier Curve of IRC-Assessed PFS in Patients with Previously Untreated MCL in ECHO At the time of the PFS analysis, the median overall survival had not been reached in either arm with a total of 203 deaths: 97 (32%) patients in the CALQUENCE plus BR arm and 106 (35%) patients in the placebo plus BR arm had died. Figure_1
14.2Previously Treated Mantle Cell Lymphoma ACE-LY-004 The efficacy of CALQUENCE was based upon Trial LY-004 titled “An Open-label, Phase 2 Study of ACP-… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies have not been conducted with acalabrutinib. Acalabrutinib was not mutagenic in an in vitro bacterial reverse mutation (AMES) assay or clastogenic in an in vitro human lymphocyte chromosomal aberration assay or in an in vivo rat bone marrow micronucleus assay. In a fertility study in rats, there were no effects of acalabrutinib on fertility in male rats at exposures 11 times, or in female rats at exposures 9 times, the AUC observed in patients at the recommended dose of 100 mg twice daily.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies have not been conducted with acalabrutinib. Acalabrutinib was not mutagenic in an in vitro bacterial reverse mutation (AMES) assay or clastogenic in an in vitro human lymphocyte chromosomal aberration assay or in an in vivo rat bone marrow micronucleus assay. In a fertility study in rats, there were no effects of acalabrutinib on fertility in male rats at exposures 11 times, or in female rats at exposures 9 times, the AUC observed in patients at the recommended dose of 100 mg twice daily.
📄 Patient Package Insert ▾
PATIENT INFORMATION PATIENT INFORMATION CALQUENCE ® (KAL-kwens) (acalabrutinib) tablets What is CALQUENCE? CALQUENCE is a prescription medicine used to treat adults with: • Mantle cell lymphoma (MCL) in combination with bendamustine and rituximab in people who have not had prior treatment for MCL and who cannot receive a type of stem cell transplant that uses their own blood stem cells (autologous hematopoietic stem cell transplantation). • Mantle cell lymphoma (MCL) who have received at least one prior therapy. • Chronic lymphocytic leukemia (CLL) or small lymphocytic lymphoma (SLL).
It is not known if CALQUENCE is safe and effective in children. Before taking CALQUENCE, tell your healthcare provider about all of your medical conditions, including if you: • have had recent surgery or plan to have surgery. Your healthcare provider may stop CALQUENCE for any planned medical, surgical, or dental procedure. • have bleeding problems. • have or had heart rhythm problems. • have an infection. • have or had liver problems, including hepatitis B virus (HBV) infection. • are pregnant or plan to become pregnant.
CALQUENCE may harm your unborn baby and cause problems during childbirth (dystocia). Females who are able to become pregnant: ∘ Your healthcare provider may do a pregnancy test before you start treatment with CALQUENCE. ∘ Use effective birth control (contraception) during treatment with CALQUENCE and for 1 week after the last dose of CALQUENCE. • are breastfeeding or plan to breastfeed. It is not known if CALQUENCE passes into your breast milk.
Do not breastfeed during treatment with CALQUENCE and for 2 weeks after your last dose of CALQUENCE. Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. Taking CALQUENCE with certain other medications may affect how CALQUENCE works and can cause side effects.
Especially tell your healthcare provider if you take a blood thinner medicine. How should I take CALQUENCE? • Take CALQUENCE exactly as your healthcare provider tells you to take it. • Do not change your dose or stop taking CALQUENCE unless your healthcare provider tells you to. • Your healthcare provider may tell you to decrease your dose, temporarily stop, or completely stop taking CALQUENCE if you develop certain side effects. • Do not switch (interchange) your CALQUENCE tablets with CALQUENCE capsules. • Take CALQUENCE 2 times a day (about 12 hours apart). • Take CALQUENCE with or without food. • Swallow CALQUENCE tablets whole with a glass of water.
Do not chew, crush, dissolve, or cut tablets. • If you miss a dose of CALQUENCE, take it as soon as you remember. If it is more than 3 hours past your usual dosing time, skip the missed dose and take your next dose of CALQUENCE at your regularly scheduled time. Do not take an extra dose to make up for a missed dose.
What are the possible side effects of CALQUENCE? CALQUENCE can cause serious side effects, including: • Serious infections have happened in people treated with CALQUENCE and may lead to death. Your healthcare provider may prescribe certain medicines if you have an increased risk of getting infections.
Tell your healthcare provider right away if you have any signs or symptoms of an infection, including fever, chills, or flu-like symptoms. • Bleeding problems (hemorrhage) have happened in people treated with CALQUENCE and can be serious and may lead to death. Your risk of bleeding may increase if you are also taking a blood thinner medicine. Tell your healthcare provider right away if you have any signs or symptoms of bleeding, including: ∘ blood in your stools or black stools (looks like tar) ∘ pink or brown urine ∘ unexpected bleeding, or bleeding that is severe or you cannot control ∘ vomit blood or vomit that looks like coffee grounds ∘ cough up blood or blood clots ∘ dizziness ∘ weakness ∘ confusion ∘ changes in your speech ∘ headache that lasts a long time ∘ bruising o… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Dosage and Administration, Recommended Dosage (2.1) 2/2026 Dosage and Administration, Dosage Modifications for Adverse Reactions (2.3) 2/2026 Warnings and Precautions, Serious and Opportunistic Infections (5.1) 2/2026
📄 Package Label / Principal Display Panel ▾
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL NDC 0310-3512-60 CALQUENCE ® (acalabrutinib) tablets 100 mg Rx only Do not chew, crush, dissolve, or cut tablets Manufactured for: AstraZeneca Pharmaceuticals LP Wilmington, DE 19850 By: AstraZeneca AB SE-151 85 Södertälje Sweden Product of Switzerland 100mg_60_tablet_bottle
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL NDC 0310-4513-60 CALQUENCE ® (acalabrutinib) tablets 100 mg Rx only Do not chew, crush, dissolve, or cut tablets Manufactured for: AstraZeneca Pharmaceuticals LP Wilmington, DE 19850 AstraZeneca 60 tablets 100_mg
Medicaid utilization & spend
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |