
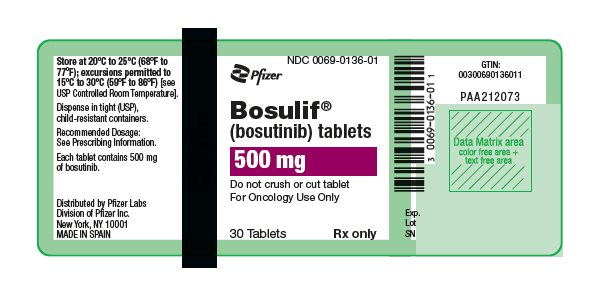
BOSULIF Bosutinib 500 mg Tablet, Film Coated, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- You have a type of leukemia called Ph+ CML, which is driven by a faulty protein in your blood cells called BCR-ABL. Think of it like a stuck 'on' switch that keeps telling those ce...
- What exactly is bosutinib treating in my body?
- Yes — this is actually pretty important. Food significantly increases how much of the medicine your body absorbs, so taking it on an empty stomach means you'd be getting much less...
- Do I have to take it with food every single time?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Bosutinib — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII K0KQV10C35
Povidone K25 is a synthetic polymer made from vinyl pyrrolidone. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach for better absorption.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $696.64 | $20,899.15 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $723.69 | $21,710.68 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Bosulif 500 mgthis 00069-0136-01 | Pfizer | 30 tablets | — | AB | FDA listed | — |
| Bosutinib 500 mg 46708-0312-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Bosutinib 500 mg 62332-0312-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 7417148 ↗ | Method of use | U-1283 | Dec 11, 2025 |
| US 7417148 ↗ | Method of use | U-1283 | Dec 11, 2025 |
| US 7417148 ↗ | Method of use | U-1283 | Dec 11, 2025 |
| US 7417148 ↗ | Method of use | U-3708 | Dec 11, 2025 |
| US 7417148 ↗ | Method of use | U-3707 | Dec 11, 2025 |
| US 7417148 ↗ | Method of use | U-3707 | Dec 11, 2025 |
| US 7417148 ↗ | Method of use | U-3708 | Dec 11, 2025 |
| US 7417148 ↗ | Method of use | U-3708 | Dec 11, 2025 |
| US 7417148 ↗ | Method of use | U-3707 | Dec 11, 2025 |
| US 11103497 ↗ | Method of use | U-3216 | Feb 28, 2034 |
| US 11103497 ↗ | Method of use | U-3216 | Feb 28, 2034 |
| US 11103497 ↗ | Method of use | U-3216 | Feb 28, 2034 |
| US 11103497 ↗ | Method of use | U-3217 | Feb 28, 2034 |
| US 11103497 ↗ | Method of use | U-3217 | Feb 28, 2034 |
| US 11103497 ↗ | Method of use | U-3217 | Feb 28, 2034 |
| US 7767678 ↗ | Drug substance | — | Nov 23, 2026 |
| US 7919625 ↗ | Drug product | — | Dec 11, 2025 |
| US 7767678 ↗ | Drug substance | — | Nov 23, 2026 |
| US 7919625 ↗ | Drug product | — | Dec 11, 2025 |
| US 7919625 ↗ | Drug product | — | Dec 11, 2025 |
| US 7767678 ↗ | Drug substance | — | Nov 23, 2026 |
| US 7417148*PED ↗ | Drug product | — | Jun 11, 2026 |
| US 7767678*PED ↗ | Drug product | — | May 23, 2027 |
| US 7919625*PED ↗ | Drug product | — | Jun 11, 2026 |
| US 7417148*PED ↗ | Drug product | — | Jun 11, 2026 |
| US 7767678*PED ↗ | Drug product | — | May 23, 2027 |
| US 7919625*PED ↗ | Drug product | — | Jun 11, 2026 |
| US 7919625*PED ↗ | Drug product | — | Jun 11, 2026 |
| US 7767678*PED ↗ | Drug product | — | May 23, 2027 |
| US 7417148*PED ↗ | Drug product | — | Jun 11, 2026 |
| US 11103497*PED ↗ | Drug product | — | Aug 28, 2034 |
| US 11103497*PED ↗ | Drug product | — | Aug 28, 2034 |
| US 11103497*PED ↗ | Drug product | — | Aug 28, 2034 |
| Code | What it grants | Expires |
|---|---|---|
| I-923 | New indication (3-year) | Sep 26, 2026 |
| ODE-444 | Orphan Drug Exclusivity (7-year) | Sep 26, 2030 |
| I-923 | New indication (3-year) | Sep 26, 2026 |
| ODE-444 | Orphan Drug Exclusivity (7-year) | Sep 26, 2030 |
| I-923 | New indication (3-year) | Sep 26, 2026 |
| ODE-444 | Orphan Drug Exclusivity (7-year) | Sep 26, 2030 |
| PED | Pediatric Exclusivity (+6 months) | Mar 26, 2031 |
| PED | Pediatric Exclusivity (+6 months) | Mar 26, 2031 |
| PED | Pediatric Exclusivity (+6 months) | Mar 26, 2031 |
| PED | Pediatric Exclusivity (+6 months) | Mar 26, 2027 |
| PED | Pediatric Exclusivity (+6 months) | Mar 26, 2027 |
| PED | Pediatric Exclusivity (+6 months) | Mar 26, 2027 |
Is there a generic version of BOSULIF 500 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00069-0136-01 You're viewing this | 30 TABLET, FILM COATED in 1 BOTTLE (0069-0136-01) | 2012-09-04 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE BOSULIF is indicated for the treatment of: • Adult and pediatric patients 1 year of age and older with chronic phase (CP) Philadelphia chromosome-positive chronic myelogenous leukemia (Ph+ CML), newly-diagnosed or resistant or intolerant to prior therapy [see Clinical Studies ( 14.1 , 14.2 , 14.3 )] . • Adult patients with accelerated phase (AP), or blast phase (BP) Ph+ CML with resistance or intolerance to prior therapy [see Clinical Studies (14.2) ] . BOSULIF is a kinase inhibitor indicated for the treatment of • adult and pediatric patients 1 year of age and older with chronic phase Ph+ chronic myelogenous leukemia (CML), newly-diagnosed or resistant or intolerant to prior therapy.
( 1 ) • adult patients with accelerated, or blast phase Ph+ CML with resistance or intolerance to prior therapy. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Adult patients with newly-diagnosed chronic phase Ph+ CML: 400 mg orally once daily with food. ( 2.1 ) • Adult patients with chronic, accelerated, or blast phase Ph+ CML with resistance or intolerance to prior therapy: 500 mg orally once daily with food. ( 2.1 ) • Pediatric patients with newly-diagnosed chronic phase Ph+ CML: 300 mg/m 2 orally once daily with food.
( 2.1 ) • Pediatric patients with chronic phase Ph+ CML with resistance or intolerance to prior therapy: 400 mg/m 2 orally once daily with food. ( 2.1 ) • Consider dose escalation by increments of 100 mg once daily to a maximum of 600 mg daily in adult patients who do not reach complete hematologic, cytogenetic, or molecular response and do not have Grade 3 or greater adverse reactions. ( 2.2 ) • Consider dose escalation by increments of 50 mg for those with a BSA <1.1 m 2 and 100 mg for those with a BSA ≥1.1 m 2 to a maximum of 600 mg daily in pediatric patients who do not reach sufficient response after 3 months.
( 2.2 ) • Adjust dosage for toxicity and organ impairment ( 2 )
2.1Recommended Dosage The recommended dosage is taken orally once daily with food. Swallow tablets whole. Do not cut, crush, break or chew tablets.
Continue treatment with BOSULIF until disease progression or intolerance to therapy. Capsules may be swallowed whole. For patients who are unable to swallow a whole capsule(s), each capsule can be opened and the contents mixed with applesauce or yogurt.
Mixing the capsule contents with applesauce or yogurt cannot be considered a substitute of a proper meal. If a dose is missed beyond 12 hours, the patient should skip the dose and take the usual prescribed dose on the following day. Dosage in Adult Patients with Newly-Diagnosed CP Ph+ CML The recommended dosage of BOSULIF is 400 mg orally once daily with food.
Dosage in Adult Patients with CP, AP, or BP Ph+ CML with Resistance or Intolerance to Prior Therapy The recommended dosage of BOSULIF is 500 mg orally once daily with food. Dosage in Pediatric Patients with Newly-Diagnosed CP Ph+ CML or with CP Ph+ CML with Resistance or Intolerance to Prior Therapy The recommended dose of BOSULIF for pediatric patients with newly-diagnosed CP Ph+ CML is 300 mg/m 2 orally once daily with food and the recommended dosage for pediatric patients with CP Ph+ CML that is resistant or intolerant to prior therapy is 400 mg/m 2 orally once daily with food and dose recommendations are provided in Table 1.
As appropriate, the desired dose can be attained by combining different strengths of BOSULIF tablets or capsules. Table 1: Dosing of BOSULIF for Pediatric Patients with Newly-Diagnosed CP Ph+ CML or with CP Ph+ CML with Resistance or Intolerance to Prior Therapy BSA BSA=Body Surface Area Newly-Diagnosed Recommended Dose (Once Daily) Resistant or Intolerant Recommended Dose (Once Daily) < 0.55 m 2 150 mg 200 mg 0.55 to < 0.63 m 2 200 mg 250 mg 0.63 to < 0.75 m 2 200 mg 300 mg 0.75 to < 0.9 m 2 250 mg 350 mg 0.9 to < 1.1 m 2 300 mg 400 mg ≥ 1.1 m 2 400 mg maximum starting dose (corresponding to maximum starting dose in adult indication) 500 mg Preparation Instructions for BOSULIF Capsules Mixed with Applesauce or Yogurt For patients who are unable to swallow capsules, the contents of the capsules can be mixed with applesauce or yogurt.
Remove the required number of capsules from the container to prepare the dose as instructed and the amount of either room temperature applesauce or yogurt in a clean container. Carefully open each capsule, add the entire capsule content of each capsule into the applesauce or yogurt, then mix the entire dose into the applesauce or yogurt. Patients should immediately consume the full mixture in its entirety, without chewing.
Do not store the mixture for later use. If the entire preparation is not swallowed do not take an additional dose. Wait until the next day to resume dosing.
Table 2: BOSULIF Dose Using Capsules and Soft Food Volumes Dose Volume of Applesau…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: • 100 mg: yellow, oval, biconvex, film-coated tablets debossed with "Pfizer" on one side and "100" on the other. • 400 mg: orange, oval, biconvex, film-coated tablets debossed with "Pfizer" on one side and "400" on the other. • 500 mg: red, oval, biconvex, film-coated tablets debossed with "Pfizer" on one side and "500" on the other. Capsules: • 50 mg: white body/orange cap with “BOS 50” printed on the body and “Pfizer” printed on the cap in black ink. • 100 mg: white body/brownish-red cap with “BOS 100” printed on the body and “Pfizer” printed on the cap in black ink. • Tablets: 100 mg, 400 mg, and 500 mg.
( 3 ) • Capsules 50 mg, 100 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS BOSULIF is contraindicated in patients with a history of hypersensitivity to BOSULIF. Reactions have included anaphylaxis [see Adverse Reactions (6.1) ] . Hypersensitivity to BOSULIF. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Gastrointestinal Toxicity: Monitor and manage as necessary. Withhold, dose reduce, or discontinue BOSULIF. ( 2.3 , 5.1 ) • Myelosuppression: Monitor blood counts and manage as necessary.
Withhold, dose reduce, or discontinue BOSULIF. ( 2.4 , 5.2 ) • Hepatic Toxicity: Monitor liver enzymes at least monthly for the first 3 months and as needed. Withhold, dose reduce, or discontinue BOSULIF.
( 2.3 , 5.3 ) • Cardiovascular Toxicity: Monitor and manage as necessary. Interrupt, dose reduce, or discontinue BOSULIF. ( 5.4 ) • Fluid Retention: Monitor patients and manage using standard of care treatment.
Interrupt, dose reduce, or discontinue BOSULIF. ( 2.3 , 5.5 ) • Renal Toxicity: Monitor patients for renal function at baseline and during therapy with BOSULIF. ( 5.6 ) • Embryo-Fetal Toxicity: BOSULIF can cause fetal harm.
Advise female patients of reproductive potential of potential risk to a fetus and to use effective contraception. ( 5.7 )
5.1Gastrointestinal Toxicity Diarrhea, nausea, vomiting, and abdominal pain occur with BOSULIF treatment. Monitor and manage patients using standards of care, including antidiarrheals, antiemetics, and fluid replacement. In the randomized clinical trial in adult patients with newly-diagnosed Ph+ CML, the median time to onset for diarrhea (all grades) was 4 days and the median duration per event was 3 days.
Among 546 adult patients in a single-arm study in patients with CML who were resistant or intolerant to prior therapy, the median time to onset for diarrhea (all grades) was 2 days and the median duration per event was 2 days. Among the patients who experienced diarrhea, the median number of episodes of diarrhea per patient during treatment with BOSULIF was 3 (range 1–268). Among 49 pediatric patients with newly-diagnosed CP Ph+ CML or who had CP Ph+ CML that was resistant or intolerant to prior therapy, the median time to onset for diarrhea (all grades) was 2 days and the duration was 2 days.
Among patients who experienced diarrhea, the median number of episodes of diarrhea per patient during treatment with BOSULIF was 2 (range 1 – 198). To manage gastrointestinal toxicity, withhold, dose reduce, or discontinue BOSULIF as necessary [see Dosage and Administration (2.3) and Adverse Reactions (6) ] .
5.2Myelosuppression Thrombocytopenia, anemia and neutropenia occur with BOSULIF treatment. Perform complete blood counts weekly for the first month of therapy and then monthly thereafter, or as clinically indicated. To manage myelosuppression, withhold, dose reduce, or discontinue BOSULIF as necessary [see Dosage and Administration (2.4) and Adverse Reactions (6) ] .
5.3Hepatic Toxicity Bosutinib may cause elevations in serum transaminases (alanine aminotransferase [ALT], aspartate aminotransferase [AST]). Two cases consistent with drug induced liver injury (defined as concurrent elevations in ALT or AST greater than or equal to 3×ULN with total bilirubin greater than 2×ULN and alkaline phosphatase less than 2×ULN) have occurred without alternative causes. This represented 2 out 1711 patients in BOSULIF clinical trials.
In the 268 adult patients from the safety population in the randomized clinical trial in patients with newly-diagnosed CML in the BOSULIF treatment group, the incidence of ALT elevation was 68.3% and increased AST was 56%. Of patients who experienced increased transaminases of any grade, 73% experienced their first increase within the first 3 months. The median time to onset of increased ALT and AST was 29 and 56 days, respectively, and the median duration was 19 and 15 days, respectively.
Among the 546 adult patients in a single-arm study in patients with CML who were resistant or intolerant to prior therapy, the incidence of increased ALT was 53.3% and AST elevation was 46.7%. Sixty percent of the patients experienced an increase in either ALT or AST. Most cases of transaminase elevations in this study occurred early in treatment; of patients who expe…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are discussed in greater detail in other sections of the labeling: • Gastrointestinal toxicity [see Warnings and Precautions (5.1) ] . • Myelosuppression [see Warnings and Precautions (5.2) ] . • Hepatic toxicity [see Warnings and Precautions (5.3) ] . • Cardiovascular toxicity [see Warnings and Precautions (5.4) ] . • Fluid retention [see Warnings and Precautions (5.5) ] . • Renal toxicity [see Warnings and Precautions (5.6) ] . • Most common adverse reactions (≥20%), in adult and pediatric patients with CML are diarrhea, abdominal pain, vomiting, nausea, rash, fatigue, hepatic dysfunction, headache, pyrexia, decreased appetite respiratory tract infection, and constipation.
The most common laboratory abnormalities (≥20%) in adult and pediatric patients are creatinine increased, hemoglobin decreased, lymphocyte count decreased, platelets decreased, ALT increased, calcium decreased, white blood cell count decreased, AST increased, absolute neutrophil count decreased, glucose increased, phosphorus decreased, urate increased, alkaline phosphatase increased, lipase increased, creatine kinase increased, and amylase increased. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Pfizer Inc. at 1-800-438-1985 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The most common adverse reactions, in ≥20% of adults with newly diagnosed CP Ph+ CML or CP, AP, or BP Ph+ CML with resistance or intolerance to prior therapy (N=814) were diarrhea (80%), rash (44%), nausea (44%), abdominal pain (43%), vomiting (33%), fatigue (33%), hepatic dysfunction (33%), respiratory tract infection (25%), pyrexia (24%), and headache (21%).
The most common laboratory abnormalities that worsened from baseline in ≥20% of adults were creatinine increased (93%), hemoglobin decreased (90%), lymphocyte count decreased (72%), platelets decreased (69%), ALT increased (58%), calcium decreased (53%), white blood cell count decreased (52%), absolute neutrophils count decreased (50%), AST increased (50%), glucose increased (46%), phosphorus decreased (44%), urate increased (41%), alkaline phosphatase increased (40%), lipase increased (36%), creatine kinase increased (29%), and amylase increased (24%).
The most common adverse reactions, in ≥20% of pediatric patients (N=49) were diarrhea (82%), abdominal pain (73%), vomiting (55%), nausea (49%), rash (49%), fatigue (37%), hepatic dysfunction (37%), headache (35%), pyrexia (31%), decreased appetite (27%), and constipation (20%). The most common laboratory abnormalities that worsened from baseline in ≥20% of pediatric patients were creatinine increased (92%), alanine aminotransferase increased (59%), white blood cell count decreased (53%), aspartate aminotransferase increased (51%), platelet count decreased (49%), glucose increased (41%), calcium decreased (31%), hemoglobin decreased (31%), neutrophil count decreased (31%), lymphocyte count decreased (29%), serum amylase increased (27%), and CPK increased (25%).
Adverse Reactions in Adult Patients With Newly-Diagnosed CP CML The clinical trial randomized and treated 533 patients with newly-diagnosed CP CML to receive BOSULIF 400 mg daily or imatinib 400 mg daily as single agents (Newly-Diagnosed CP CML Study) [see Clinical Studies (14.1) ] . The safety population (received at least 1 dose of BOSULIF) included: • two hundred sixty-eight (268) patients with newly-diagnosed CP CML had a median duration of BOSULIF treatment of 55 months (range: 0.3 to 60 months) and a median dose intensity of 394 mg/day.
Serious adverse reactions occurred in 22% of patients with newly-diagnosed CP CML who received bosutinib. Serio…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Strong and Moderate CYP3A Inhibitors: Avoid concomitant use with BOSULIF. ( 7.1 ) • Strong CYP3A Inducers: Avoid concomitant use with BOSULIF. ( 7.1 ) • Proton Pump Inhibitors: Use short-acting antacids or H2 blockers as an alternative to proton pump inhibitors. ( 7.1 )
7.1Effect of Other Drugs on BOSULIF Strong or Moderate CYP3A Inhibitors Avoid the concomitant use of strong or moderate CYP3A inhibitors with BOSULIF. Bosutinib is a CYP3A substrate. Concomitant use with a strong or moderate CYP3A inhibitor increases bosutinib C max and AUC [see Clinical Pharmacology (12.3) ] which may increase the risk of toxicities.
Strong CYP3A Inducers Avoid the concomitant use of strong CYP3A inducers with BOSULIF. Bosutinib is a CYP3A substrate. Concomitant use with a strong CYP3A inducer decreases bosutinib C max and AUC [see Clinical Pharmacology (12.3) ] which may reduce BOSULIF efficacy.
Proton Pump Inhibitors (PPI) As an alternative to PPIs, use short-acting antacids or H2 blockers and separate dosing by more than 2 hours from BOSULIF dosing. Bosutinib displays pH dependent aqueous solubility, Concomitant use with a PPI decreases bosutinib C max and AUC [see Clinical Pharmacology (12.3) ] which may reduce BOSULIF efficacy.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise women not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action, BOSULIF can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available data in pregnant women to inform the drug-associated risk. In animal reproduction studies conducted in rats and rabbits, oral administration of bosutinib during organogenesis caused adverse developmental outcomes, including structural abnormalities, embryo-fetal mortality, and alterations to growth at maternal exposures (AUC) as low as 1.2 times the human exposure at the dose of 500 mg/day ( see Data ).
Advise pregnant women of the potential risk to a fetus. The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies are 2–4% and 15–20%, respectively. Data Animal Data In a rat fertility and early embryonic development study, bosutinib was administered orally to female rats for approximately 3 to 6 weeks, depending on day of mating (2 weeks prior to cohabitation with untreated breeder males until gestation day [GD] 7). Increased embryonic resorptions occurred at greater than or equal to 10 mg/kg/day of bosutinib (1.6 and 1.2 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively), and decreased implantations and reduced number of viable embryos at 30 mg/kg/day of bosutinib (3.4 and 2.5 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively).
In an embryo-fetal development study conducted in rabbits, bosutinib was administered orally to pregnant animals during the period of organogenesis at doses of 3, 10, and 30 mg/kg/day. At the maternally-toxic dose of 30 mg/kg/day of bosutinib, there were fetal anomalies (fused sternebrae, and 2 fetuses had various visceral observations), and an approximate 6% decrease in fetal body weight. The dose of 30 mg/kg/day resulted in exposures (AUC) approximately 5.1 and 3.8 times the human exposures at the recommended doses of 400 and 500 mg/day, respectively.
Fetal exposure to bosutinib-derived radioactivity during pregnancy was demonstrated in a placental-transfer study in pregnant rats. In a rat pre- and postnatal development study, bosutinib was administered orally to pregnant animals during the period of organogenesis through lactation day 20 at doses of 10, 30, and 70 mg/kg/day. Reduced number of pups born occurred at greater than or equal to 30 mg/kg/day bosutinib (3.4 and 2.5 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively), and increased incidence of total litter loss and decreased growth of offspring after birth occurred at 70 mg/kg/day bosutinib (6.9 and 5.1 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively).
8.2Lactation Risk Summary No data are available regarding the presence of bosutinib or its metabolites in human milk or its effects on a breastfed child or on milk production. However, bosutinib is present in the milk of lactating rats. Because of the potential for serious adverse reactions in a nursing child, breastfeeding is not recommended during treatment with BOSULIF and for 2 weeks after the last dose.
Animal Data After a single radiolabeled bosutinib dose to lactating rats, radioactivity was present in the plasma of suckling offspring for 24 to 48 hours.
8.3Females and Males of Reproductive Potential Based on findings from animal studies, BOSULIF can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Pregnancy Females of reproductive potential should have a pregnancy test prior to starting treatment with BOSULIF. Contraception Females Adv…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action, BOSULIF can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available data in pregnant women to inform the drug-associated risk. In animal reproduction studies conducted in rats and rabbits, oral administration of bosutinib during organogenesis caused adverse developmental outcomes, including structural abnormalities, embryo-fetal mortality, and alterations to growth at maternal exposures (AUC) as low as 1.2 times the human exposure at the dose of 500 mg/day ( see Data ).
Advise pregnant women of the potential risk to a fetus. The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies are 2–4% and 15–20%, respectively. Data Animal Data In a rat fertility and early embryonic development study, bosutinib was administered orally to female rats for approximately 3 to 6 weeks, depending on day of mating (2 weeks prior to cohabitation with untreated breeder males until gestation day [GD] 7). Increased embryonic resorptions occurred at greater than or equal to 10 mg/kg/day of bosutinib (1.6 and 1.2 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively), and decreased implantations and reduced number of viable embryos at 30 mg/kg/day of bosutinib (3.4 and 2.5 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively).
In an embryo-fetal development study conducted in rabbits, bosutinib was administered orally to pregnant animals during the period of organogenesis at doses of 3, 10, and 30 mg/kg/day. At the maternally-toxic dose of 30 mg/kg/day of bosutinib, there were fetal anomalies (fused sternebrae, and 2 fetuses had various visceral observations), and an approximate 6% decrease in fetal body weight. The dose of 30 mg/kg/day resulted in exposures (AUC) approximately 5.1 and 3.8 times the human exposures at the recommended doses of 400 and 500 mg/day, respectively.
Fetal exposure to bosutinib-derived radioactivity during pregnancy was demonstrated in a placental-transfer study in pregnant rats. In a rat pre- and postnatal development study, bosutinib was administered orally to pregnant animals during the period of organogenesis through lactation day 20 at doses of 10, 30, and 70 mg/kg/day. Reduced number of pups born occurred at greater than or equal to 30 mg/kg/day bosutinib (3.4 and 2.5 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively), and increased incidence of total litter loss and decreased growth of offspring after birth occurred at 70 mg/kg/day bosutinib (6.9 and 5.1 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of BOSULIF have been established in pediatric patients 1 year of age and older with newly-diagnosed CP Ph+ CML and CP Ph+ CML that is resistant or intolerant to prior therapy. Use of BOSULIF for these indications is based on data from BCHILD [NCT04258943]. The study included pediatric patients with newly diagnosed CP Ph+ CML in the following age groups: 2 patients 1 year of age to less than 6 years of age, 3 patients 6 years of age to less than 12 years of age, and 10 patients 12 years of age to less than 17 years of age.
The study also included pediatric patients with CP Ph+ CML that was resistant or intolerant to prior therapy in the following age groups: 4 patients 1 year of age to less than 6 years of age, 10 patients 6 years of age to less than 12 years of age, and 10 patients 12 years of age to less than 17 years of age [see Adverse Reactions (6.1) and Clinical Studies (14.3) ] . BSA-normalized apparent clearance in 27 pediatric patients aged 4 to <17 years (141.3 L/h/m 2 ) was 29% higher than BSA-normalized apparent clearance in adult patients with CP Ph+ CML (109.2 L/h/m 2 ) [see Clinical Pharmacology (12.3) ] .
The recommended dosage of BOSULIF in pediatric patients is based on body surface area (BSA) [see Dosage and Administration (2.1) ]. The safety and effectiveness of BOSULIF in pediatric patients younger than 1 year of age with newly diagnosed CP Ph+ CML, pediatric patients younger than 1 year of age with CP Ph+ CML that is resistant or intolerant to prior therapy, and pediatric patients with AP Ph+ CML or BP Ph+ CML have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use In the single-arm study in patients with CML who were resistant or intolerant to prior therapy of BOSULIF in patients with Ph+ CML, 20% were age 65 and over, 4% were 75 and over. Of the 268 patients who received bosutinib in the study for newly diagnosed CML, 20% were age 65 and over, 5% were 75 and over. No overall differences in safety or effectiveness were observed between these patients and younger patients, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE Experience with BOSULIF overdose in clinical studies was limited to isolated cases. There were no reports of any serious adverse events associated with the overdoses. Patients who take an overdose of BOSULIF should be observed and given appropriate supportive treatment.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Bosutinib is a TKI. Bosutinib inhibits the BCR-ABL kinase that promotes CML; it is also an inhibitor of Src-family kinases including Src, Lyn, and Hck. Bosutinib inhibited 16 of 18 imatinib-resistant forms of BCR-ABL kinase expressed in murine myeloid cell lines. Bosutinib did not inhibit the T315I and V299L mutant cells.
12.2Pharmacodynamics A greater likelihood of response and a greater likelihood of safety events were observed with higher bosutinib exposure in clinical studies. The time course of bosutinib pharmacodynamic response has not been fully characterized. Cardiac Electrophysiology At a single oral dose of 500 mg BOSULIF with ketoconazole (a strong CYP3A inhibitor), BOSULIF does not prolong the QT interval to any clinically relevant extent.
12.3Pharmacokinetics Bosutinib pharmacokinetics were assessed following oral dosing with food in adult patients with CML and were presented as geometric mean (CV%), unless otherwise specified. Bosutinib exhibits dose proportional increases in C max and AUC over the oral dose range of 200 to 800 mg (0.33 to 1.3 times the maximum approved recommended dosage of 600 mg). Bosutinib steady state C max was 127 ng/mL (31%), C trough was 68 ng/mL (39%) and AUC was 2370 ng•h/mL (34%) following multiple oral doses of BOSULIF 400 mg; Bosutinib steady state C max was 171 ng/mL (38%), C trough was 91 ng/mL (42%) and AUC was 3150 ng•h/mL (38%) following multiple oral doses of BOSULIF 500 mg.
No clinically significant differences in the pharmacokinetics of bosutinib were observed following administration of either the tablet or capsule dosage forms of BOSULIF at the same dose, under fed conditions. Absorption The median bosutinib (minimum, maximum) time-‑to-C max (t max ) was 6.0 (6.0, 6.0) hours following oral administration of a single oral dose of BOSULIF 500 mg with food. The absolute bioavailability was 34% in healthy subjects.
Effect of Food Bosutinib C max increased 1.8-fold and AUC increased 1.7-fold when BOSULIF tablets were given with a high fat meal to healthy subjects compared to administration under fasted condition. Bosutinib C max increased 1.6‑fold and AUC increased 1.5-fold when BOSULIF capsules were given with a high fat meal to healthy subjects compared to administration under fasted condition. The high-fat meal (800-1000 total calories) consisted of approximately 150 protein calories, 250 carbohydrate calories, and 500-600 fat calories.
No clinically significant differences in the pharmacokinetics of bosutinib were observed following administration of a BOSULIF capsule that was opened and the contents mixed with applesauce or yogurt immediately before use. Distribution The mean (SD) apparent bosutinib volume of distribution is 6080 (1230) L after an oral dose of 500 mg of BOSULIF. Bosutinib protein binding is 94% in vitro and 96% ex vivo , and is independent of concentration.
Elimination The mean (SD) bosutinib terminal phase elimination half life (t ½ ) was 22.5 (1.7) hours, and the mean (SD) apparent clearance was 189 (48) L/h following a single oral dose of BOSULIF. Metabolism Bosutinib is primarily metabolized by CYP3A4. Excretion Following a single oral dose of [ 14 C] radiolabeled bosutinib without food, 91.3% of the dose was recovered in feces and 3.3% of the dose recovered in urine.
Specific Populations Patients with Renal Impairment Bosutinib AUC increased 1.4-fold in subjects with moderate renal impairment (CL cr : 30 to 50 mL/min, estimated by Cockcroft-Gault (C-G)) and increased 1.6-fold in subjects with severe renal impairment (CL cr less than 30 mL/min) following a single oral dose of BOSULIF 200 mg (0.33 times the maximum approved recommended dosage of 600 mg). No clinically significant difference in the pharmacokinetics of bosutinib was observed in subjects with mild renal impairment (CL cr : 51 to 80 mL/min, C-G) .
BOSULIF has not been studied in patients undergoing hemodialysis. Patients with Hepatic Impair…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Bosutinib is a TKI. Bosutinib inhibits the BCR-ABL kinase that promotes CML; it is also an inhibitor of Src-family kinases including Src, Lyn, and Hck. Bosutinib inhibited 16 of 18 imatinib-resistant forms of BCR-ABL kinase expressed in murine myeloid cell lines. Bosutinib did not inhibit the T315I and V299L mutant cells.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Tablets – How Supplied BOSULIF (bosutinib) tablets are supplied for oral administration in 3 strengths: a 100 mg yellow, oval, biconvex, film-coated tablet debossed with "Pfizer" on one side and "100" on the other; a 400 mg orange, oval, biconvex, film coated tablet debossed with "Pfizer" on one side and "400" on the other; and a 500 mg red, oval, biconvex, film-coated tablet debossed with "Pfizer" on one side and "500" on the other. BOSULIF (bosutinib) tablets are available in the following packaging configurations with a child-resistant (CR) closure (Table 17).
Bottles contain a desiccant. Table 17: Tablet Presentations BOSULIF Tablets Package Configuration Tablet Strength (mg) NDC Tablet Description Abbreviation: NDC=National drug code. 120 tablets per bottle 100 mg 0069-0135-01 Yellow, oval, biconvex, film-coated tablets, debossed "Pfizer" on one side and "100" on the other.
30 tablets per bottle 400 mg 0069-0193-01 Orange, oval, biconvex, film-coated tablet debossed with "Pfizer" on one side and "400" on the other. 30 tablets per bottle 500 mg 0069-0136-01 Red, oval, biconvex, film-coated tablets, debossed "Pfizer" on one side and "500" on the other. Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Handling and Disposal Procedures for proper disposal of anticancer drugs should be considered. Touching or handling crushed or broken tablets is to be avoided. Any unused product or waste material should be disposed of in accordance with local requirements, or drug take back programs.
Capsules - How Supplied BOSULIF (bosutinib) capsules are supplied for oral administration in 2 strengths: 50 mg capsule: size 2 capsule, white body/orange cap with “BOS 50” printed on the body and “Pfizer” printed on the cap in black ink. 100 mg capsule: size 0 capsule, white body/brownish-red cap with “BOS 100” printed on the body and “Pfizer” printed on the cap in black ink. BOSULIF (bosutinib) capsules are available in the following packaging configurations with a CR closure (Table 18).
Table 18: Capsule Presentations Abbreviation: NDC=National drug code. BOSULIF Capsules Package Configuration Count Capsule Strength (mg) NDC Capsule Description 30 capsules per bottle 50 0069-0504-30 Size 2 capsule, white body/orange cap with “BOS 50” printed on the body and “Pfizer” printed on the cap in black ink. 150 capsules per bottle 100 0069-1014-15 Size 0 capsule, white body/brownish-red cap with “BOS 100” printed on the body and “Pfizer” printed on the cap in black ink.
Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature] and Store and Dispense in Original Container. Handling and Disposal Procedures for proper disposal of anticancer drugs should be considered. Patients and/or caregivers must wear gloves while handling the drug product, and wash their hands once finished.
Any unused product or waste material should be disposed of in accordance with local requirements.
📦 Storage and Handling ▾
Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Handling and Disposal Procedures for proper disposal of anticancer drugs should be considered. Touching or handling crushed or broken tablets is to be avoided. Any unused product or waste material should be disposed of in accordance with local requirements, or drug take back programs.
Capsules - How Supplied BOSULIF (bosutinib) capsules are supplied for oral administration in 2 strengths: 50 mg capsule: size 2 capsule, white body/orange cap with “BOS 50” printed on the body and “Pfizer” printed on the cap in black ink. 100 mg capsule: size 0 capsule, white body/brownish-red cap with “BOS 100” printed on the body and “Pfizer” printed on the cap in black ink. BOSULIF (bosutinib) capsules are available in the following packaging configurations with a CR closure (Table 18).
Table 18: Capsule Presentations Abbreviation: NDC=National drug code. BOSULIF Capsules Package Configuration Count Capsule Strength (mg) NDC Capsule Description 30 capsules per bottle 50 0069-0504-30 Size 2 capsule, white body/orange cap with “BOS 50” printed on the body and “Pfizer” printed on the cap in black ink. 150 capsules per bottle 100 0069-1014-15 Size 0 capsule, white body/brownish-red cap with “BOS 100” printed on the body and “Pfizer” printed on the cap in black ink.
Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature] and Store and Dispense in Original Container. Handling and Disposal Procedures for proper disposal of anticancer drugs should be considered. Patients and/or caregivers must wear gloves while handling the drug product, and wash their hands once finished.
Any unused product or waste material should be disposed of in accordance with local requirements.
📋 Description ▾
11 DESCRIPTION BOSULIF contains bosutinib, a kinase inhibitor. Bosutinib is present as a monohydrate with a chemical name of 3-Quinolinecarbonitrile, 4-[(2,4-dichloro-5-methoxyphenyl)amino]-6-methoxy-7-[3-(4-methyl-1-piperazinyl) propoxy]-, hydrate (1:1). Its chemical formula is C 26 H 29 Cl 2 N 5 O 3 ∙H 2 O (monohydrate); its molecular weight is 548.46 (monohydrate), equivalent to 530.46 (anhydrous).
Bosutinib monohydrate has the following chemical structure: Bosutinib monohydrate is a white to yellowish-tan powder. Bosutinib monohydrate has a pH dependent solubility across the physiological pH range. At or below pH 5, bosutinib monohydrate behaves as a highly soluble compound.
Above pH 5, the solubility of bosutinib monohydrate reduces rapidly. BOSULIF ® (bosutinib) tablets are supplied for oral administration in 3 strengths: 100 mg, 400 mg and 500 mg. Each strength reflects the equivalent amount of bosutinib content (on anhydrous basis).
The tablets contain the following inactive ingredients: croscarmellose sodium, iron oxide red (for 400 mg, and 500 mg tablet) and iron oxide yellow (for 100 mg, and 400 mg tablet), magnesium stearate, microcrystalline cellulose, poloxamer, polyethylene glycol, polyvinyl alcohol, povidone, talc and titanium dioxide. BOSULIF ® (bosutinib) capsules are supplied for oral administration in 2 strengths: 50 mg and 100 mg. Each strength reflects the equivalent amount of bosutinib (on anhydrous basis).
The capsules contain the following inactive ingredients: croscarmellose sodium, gelatin, magnesium stearate, mannitol, microcrystalline cellulose, poloxamer, povidone, red iron oxide, titanium dioxide, yellow iron oxide. The printing ink contains black iron oxide, potassium hydroxide, propylene glycol, shellac, strong ammonia solution. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). • Dosage and Administration Instruct patients to take BOSULIF exactly as prescribed, not to change their dose or to stop taking BOSULIF unless they are told to do so by their doctor. If patients miss a dose beyond 12 hours, they should be advised to take the next scheduled dose at its regular time. A double dose should not be taken to make up for any missed dose.
Advise patients to take BOSULIF with food. Patients should be advised: “Swallow tablets whole. Do not crush, break, or cut tablet.
Do not touch or handle crushed or broken tablets.” Patients should be advised: “Capsules may be swallowed whole. For those that cannot swallow the capsule whole, the capsule can be opened and the contents mixed with applesauce or yogurt.” • Gastrointestinal Toxicity Advise patients that they may experience diarrhea, nausea, vomiting, abdominal pain, or blood in their stools with BOSULIF and to seek medical attention promptly for these symptoms [see Warnings and Precautions (5.1) ] . • Myelosuppression Advise patients of the possibility of developing low blood cell counts and to immediately report fever, any suggestion of infection, or signs or symptoms suggestive of bleeding or easy bruising [see Warnings and Precautions (5.2) ] . • Hepatic Toxicity Advise patients of the possibility of developing liver function abnormalities and to immediately report jaundice [see Warnings and Precautions (5.3) ] . • Cardiovascular Toxicity Advise patients that cardiac failure, left ventricular dysfunction, and cardiac ischemic events have been reported.
Advise patients to seek immediate medical attention if any symptoms suggestive of cardiac failure and cardiac ischemia occur, such as shortness of breath, weight gain, or fluid retention [see Warnings and Precautions (5.4) ] . • Fluid Retention Advise patients of the possibility of developing fluid retention (swelling, weight gain, or shortness of breath) and to seek medical attention promptly if these symptoms arise [see Warnings and Precautions (5.5) ] . • Renal Toxicity Advise patients of the possibility of developing renal problems and to immediately report frequent urination, polyuria or oliguria [see Warnings and Precautions (5.6) ] . • Adverse Reactions Advise patients that they may experience other adverse reactions such as respiratory tract infections, rash, fatigue, loss of appetite, headache, dizziness, back pain, arthralgia, pruritus or constipation with BOSULIF and to seek medical attention if symptoms are significant.
There is a possibility of anaphylactic shock [see Contraindications (4) and Adverse Reactions (6) ] . • Embryo-Fetal Toxicity Advise females to inform their healthcare provider if they are pregnant or become pregnant. Advise female patients of the risk to a fetus and potential loss of the pregnancy [see Use in Specific Populations (8.1) ] . Advise females of reproductive potential, to use effective contraception during treatment and for 2 weeks after receiving the last dose of BOSULIF [see Warnings and Precautions (5.7) and Use in Specific Populations (8.1 , 8.3) ] .
Advise lactating women not to breastfeed during treatment with BOSULIF and for 2 weeks after the last dose [see Use in Specific Populations (8.2) ] . • Drug Interactions Advise patients that BOSULIF and certain other medicines, including over the counter medications or herbal supplements (such as St. John's wort) can interact with each other and may alter the effects of BOSULIF [see Drug Interactions (7) ].