
CogniFactors Ingredients & Drug Interactions
by Nutra BioGenesis
What is this page for?
First and foremost: checking CogniFactors against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
CogniFactors is a dietary supplement by Nutra BioGenesis with 9 active ingredients. Its ingredients are commonly taken for diabetic nerve pain (neuropathy), blood sugar support in diabetes, antioxidant support.Based on those ingredients, 1,721 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Green Tea Leaf Extract, Ginkgo Leaf Extract, Bacopa Leaf Extract. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against CogniFactors by Nutra BioGenesis
Ask about any prescription or over-the-counter medication and we check it for interactions with CogniFactors by Nutra BioGenesis — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of CogniFactors by Nutra BioGenesis
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
CogniFactors contains nine active ingredients aimed at supporting cognitive health. R-alpha-lipoic acid and N-acetyl-L-carnitine are amino acid derivatives with roles in energy and nerve function.
Dimethylaminoethanol bitartrate (deanol), phosphatidylserine, and huperzine A are compounds that support brain cell signaling. Nattokinase is an enzyme derived from fermented soy.
Ginkgo leaf extract, green tea leaf extract, and bacopa leaf extract are plant-based concentrates, each with traditional or researched roles in brain function. The product also contains inactive ingredients including cellulose, ascorbyl palmitate, silica, and maltodextrin, which serve as capsule material and stabilizers.
Does it work?
Moderate evidence
The evidence for these ingredients is mixed. R-alpha-lipoic acid is possibly effective for diabetic nerve pain (neuropathy), high cholesterol, and weight management.
N-acetyl-L-carnitine is possibly effective for age-related cognitive decline, Alzheimer disease, alcohol use disorder, diabetic neuropathy, and depression. Ginkgo leaf extract is possibly effective for hearing loss, stroke recovery, schizophrenia, premenstrual syndrome, dementia, and anxiety, though the evidence base varies.
Green tea leaf extract is likely effective for human papillomavirus (HPV) related conditions and possibly effective for ovarian cancer and high cholesterol. For the other ingredients—nattokinase, deanol, phosphatidylserine, huperzine A, and bacopa—the evidence is either insufficient to rate or, in deanol's case, suggests it is likely ineffective for Alzheimer disease and tardive dyskinesia.
No ingredient in this product has strong evidence for general cognitive enhancement in healthy adults.
How safe is it?
Well-documented data
Most of these ingredients are generally well tolerated at typical doses, but each carries caveats. R-alpha-lipoic acid can lower blood sugar and may cause headache, nausea, heartburn, or skin rash; it's best used under medical guidance.
N-acetyl-L-carnitine is well tolerated short-term but long-term safety is unclear; it may cause agitation, dry mouth, headache, insomnia, or fishy-smelling breath. Deanol has limited safety evidence and can cause constipation, diarrhea, drowsiness, nausea, or mood changes, especially at higher doses.
Nattokinase may increase bleeding and can cause rare severe allergic reactions in people sensitive to natto. Phosphatidylserine is well tolerated in studies but long-term data are limited; gastrointestinal upset, insomnia, and headache are the main reported effects.
Ginkgo is generally tolerated for up to six years but carries a documented risk of bleeding and rare cardiac rhythm problems; adverse effects include dizziness, gastrointestinal upset, headache, and spontaneous bleeding. Huperzine A is pharmacologically active and can cause dose-dependent cholinergic side effects like blurred vision, constipation, diarrhea, nausea, or a slower heart rate.
Green tea extract is usually safe but high-dose concentrated extracts have rarely caused liver injury; gastrointestinal upset and nausea are common with larger amounts. Bacopa is generally well tolerated in studies but long-term safety is not fully established; headache, nausea, and diarrhea are reported.
For pregnancy: safety data are insufficient or advise against use for all nine ingredients—talk with your doctor or pharmacist before considering this product if you are pregnant or breastfeeding.
Meds to double-check
Major interaction found
Before taking CogniFactors, check with your pharmacist if you take blood thinners or antiplatelet drugs (warfarin, aspirin, clopidogrel, and others)—ginkgo, nattokinase, and alpha-lipoic acid all raise bleeding risk. If you take blood pressure medications (nadolol, other beta blockers, ACE inhibitors, or other antihypertensives), let your pharmacist know, because ginkgo and nattokinase may lower blood pressure further.
Inform them about any cholesterol drugs (atorvastatin, simvastatin), seizure medications (phenytoin, valproate, ethosuximide, felbamate), thyroid hormones, HIV medications (efavirenz), diabetes drugs, antidepressants (especially serotonin-raising ones), chemotherapy, heart rhythm drugs, or any cytochrome P450-metabolized medications, since multiple ingredients here may interfere with how these work.
The bottom line
Scorecard at a glanceFully disclosed formula with some supporting evidence for its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
CogniFactors is a multi-ingredient cognitive support formula with some ingredients showing modest evidence for specific uses (like alpha-lipoic acid for nerve pain or ginkgo for dementia) and others with limited proof of benefit. The product carries substantial medication interaction risks, especially with blood thinners, blood pressure drugs, cholesterol medications, and seizure drugs.
If you take any prescription medications, check them against the interaction tool on this page before starting. Talk with your pharmacist or doctor—especially if you have bleeding risk, high cholesterol, or blood pressure concerns.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 9 of 9 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Dec 21, 2024.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about CogniFactors, straight from the product label.
| Brand | Nutra BioGenesis |
|---|---|
| Barcode (UPC) | 812806102716 |
| Net contents | 60 Vegetarian Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Dec 21, 2024 |
| DSLD ID | 322988 |
| Product type | Other Combinations |
| Supplement form | Capsule |
| Dietary claims / uses | Nutrient, All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Women (not pregnant or lactating) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
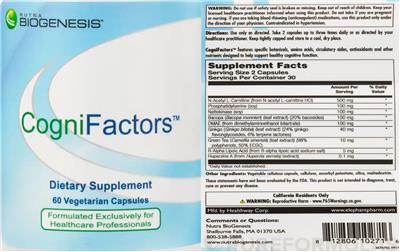
Supplement Facts
The label details for CogniFactors by Nutra BioGenesis, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| R-Alpha-Lipoic Acid | 5 mg | -- |
| N-Acetyl-L-Carnitine | 500 mg | -- |
| Dimethylaminoethanol Bitartrate | 100 mg | -- |
| Nattokinase | 100 mg | -- |
| Phosphatidylserine | 100 mg | -- |
| Ginkgo Leaf Extract | 40 mg | -- |
| Huperzine A | 0.1 mg | -- |
| Green Tea Leaf Extract | 10 mg | -- |
| Bacopa Leaf Extract | 100 mg | -- |
Other ingredients: Cellulose, Cellulose, Ascorbyl Palmitate, Silica, Maltodextrin
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
FDA Statement of Identity
Dietary Supplement
Formulation
Formulated exclusively for healthcare professionals
Precautions
Warning: Do not use if safety seal is broken or missing. Keep your licensed healthcare practitioner informed when using this product. Contraindicated in hypertension.
Keep out of reach of children.
Do not take if you are pregnant or nursing. If you are taking blood-thinning (anticoagulant) medications, use this product only under the direction of your physician.
California Residents Only Warning: Reproductive harm - www.P65Warnings.ca.gov
Suggested/Recommended/Usage/Directions
Directions: Use only as directed. Take 2 capsules up to three times daily or as directed by your healthcare practitioner.
Storage
Keep tightly capped and store in a cool, dry place.
Formula
CogniFactors features specific botanicals, amino acids, circulatory aides, antioxidants and other nutrients designed to help support healthy cognitive function.
FDA Disclaimer Statement
These statements have not been evaluated by the FDA. This product is not intended to diagnose, treat, cure or prevent any disease.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
CogniFactors by Nutra BioGenesis label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in CogniFactors by Nutra BioGenesis
These are the 9 active ingredients this product is made of. Select any to open its full monograph.
Serving size2 Capsule(s) Dosage formCapsule Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
R-Alpha-Lipoic Acid
Interacts with263 drugs
Alpha-lipoic acid (ALA) is an antioxidant made naturally by the body and found in small amounts in foods. It is most studied for diabetic nerve pain,...
R-Alpha-Lipoic Acid monograph & interactionsN-Acetyl-L-Carnitine
Interacts with203 drugs
Acetyl-L-carnitine is a form of the amino acid carnitine that the body uses to help produce energy in cells. It is most studied for nerve pain and mem...
N-Acetyl-L-Carnitine monograph & interactionsDimethylaminoethanol Bitartrate
Interacts with219 drugs
Deanol (DMAE) is a compound related to choline that is marketed for memory, focus, and mood, but solid human evidence for most of these uses is limite...
Dimethylaminoethanol Bitartrate monograph & interactionsNattokinase
Interacts with289 drugs
Nattokinase is an enzyme from the fermented soybean food natto that may have mild blood-thinning and blood-flow effects. Some small studies hint at be...
Nattokinase monograph & interactionsPhosphatidylserine
Interacts with219 drugs
Phosphatidylserine is a natural fat-like compound found in cell membranes, especially in the brain, and it is sold mainly to support memory and thinki...
Phosphatidylserine monograph & interactionsGinkgo Leaf Extract
Interacts with1,266 drugs
Ginkgo is one of the world's most popular herbal supplements, mostly taken to support memory and circulation. The evidence for these uses is mixed and...
Ginkgo Leaf Extract monograph & interactionsHuperzine A
Interacts with219 drugs
Huperzine A is a purified compound from a Chinese clubmoss that acts like a mild cholinesterase inhibitor, similar in mechanism to some prescription A...
Huperzine A monograph & interactionsGreen Tea Leaf Extract
Interacts with1,293 drugs
Green tea is a popular beverage rich in antioxidants called catechins, and drinking it in normal amounts is considered safe for most people. Concentra...
Green Tea Leaf Extract monograph & interactionsBacopa Leaf Extract
Interacts with930 drugs
Bacopa is an Ayurvedic herb most often used for memory and thinking. Some small studies suggest it may modestly help memory when taken regularly for s...
Bacopa Leaf Extract monograph & interactionsOther (inactive) ingredients: Cellulose, Cellulose, Ascorbyl Palmitate, Silica, Maltodextrin. These complete the product’s ingredient list but are not active constituents.
CogniFactors by Nutra BioGenesis Drug Interactions
HelloPharmacist Interaction Report
CogniFactors by Nutra BioGenesis contains nine active ingredients, and several of them interact with medications.
The most serious concern is ginkgo leaf extract, which significantly increases blood levels of talinolol (a beta blocker), raising the risk of excessive lowering of blood pressure and heart rate.
Read the full breakdown — every affected drug type, severity by severity
Ginkgo also interacts at major severity with two other medications: it reduces the effectiveness of nadolol (another blood pressure medication) by up to 85%, and it substantially reduces atorvastatin (a cholesterol drug) levels by about 24%. Green tea leaf extract, another ingredient here, poses major-severity interactions with nadolol (reducing its levels by roughly 85%) and atorvastatin (cutting levels by about 24%), plus it significantly increases stimulant effects when combined with ephedrine, raising the risk of serious events like heart attack, stroke, or seizure.
Moderate interactions are more numerous. R-alpha-lipoic acid theoretically increases bleeding risk with blood thinners and antiplatelet drugs, and may interfere with chemotherapy drugs, thyroid hormone replacement, and blood sugar control.
N-acetyl-L-carnitine raises concerns with blood thinners (especially warfarin and acenocoumarol), serotonin-boosting antidepressants, and thyroid hormone. Nattokinase, with documented bleeding effects, increases risk when combined with blood thinners or antiplatelet drugs and may lower blood pressure excessively with antihypertensive medications.
Ginkgo carries moderate risks with warfarin, trazodone, several HIV and diabetes drugs, seizure medications, and the heart drug tacrolimus. Huperzine A, phosphatidylserine, deanol (dimethylaminoethanol), and bacopa all theoretically interact with acetylcholine-affecting drugs—both anticholinergic and cholinergic types.
Green tea also interacts moderately with several seizure medications and the vasodilator dipyridamole. Bacopa additionally affects multiple cytochrome P450 drug-metabolizing enzymes, potentially altering levels of numerous prescription medications.
Allegedly, these interactions span 1,699 individual medications. Because the breadth of affected drugs is substantial, you must check your exact medications with the interaction checker on this page before starting CogniFactors.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against CogniFactors?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in CogniFactors interact with 1,721 drugs. Click any drug to see the details.
9 of the 9 ingredients in CogniFactors interact with drugs. Each result below shows which ingredient is responsible. Green Tea Leaf Extract Ginkgo Leaf Extract Bacopa Leaf Extract Nattokinase R-Alpha-Lipoic Acid Dimethylaminoethanol Bitartrate Phosphatidylserine Huperzine A N-Acetyl-L-Carnitine
Aminophylline, Amobarbital, EphedrineAmesec
How Aminophylline, Amobarbital, Ephedrine interacts with CogniFactors — through 2 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractEphedrine, Stimulant Drugs Major
Interaction Summary
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Read the full Green Tea Leaf Extract + Aminophylline, Amobarbital, Ephedrine interactionGinkgo Leaf ExtractAnticonvulsants Moderate
Interaction Summary
Theoretically, ginkgo might reduce the effectiveness of anticonvulsants.
Read the full Ginkgo Leaf Extract + Aminophylline, Amobarbital, Ephedrine interactionAtorvastatinAtorvaliq
How Atorvastatin interacts with CogniFactors — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractOrganic Anion-transporting Polypeptide Substrates (oatp), Cytochrome P450 3a4 (cyp3a4) Substrates +2 Major
Interaction Summary
Theoretically, green tea might reduce the absorption of organic anion-transporting polypeptide (OATP) substrates.
Read the full Green Tea Leaf Extract + Atorvastatin interactionGinkgo Leaf ExtractAtorvastatin (lipitor), Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease the levels and clinical effects of atorvastatin.
Read the full Ginkgo Leaf Extract + Atorvastatin interactionBacopa Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP3A4 substrates.
Read the full Bacopa Leaf Extract + Atorvastatin interactionAtorvastatin CalciumLipitor
How Atorvastatin Calcium interacts with CogniFactors — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractAtorvastatin (lipitor), Organic Anion-transporting Polypeptide Substrates (oatp) +2 Major
Interaction Summary
Green tea extract seems to reduce the levels and clinical effects of atorvastatin.
Read the full Green Tea Leaf Extract + Atorvastatin Calcium interactionGinkgo Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Atorvastatin (lipitor) Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Leaf Extract + Atorvastatin Calcium interactionBacopa Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP3A4 substrates.
Read the full Bacopa Leaf Extract + Atorvastatin Calcium interactionBendroflumethiazide, NadololCorzide
How Bendroflumethiazide, Nadolol interacts with CogniFactors — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractNadolol (corgard), Diuretic Drugs Major
Interaction Summary
Green tea seems to reduce the levels and clinical effects of nadolol.
Read the full Green Tea Leaf Extract + Bendroflumethiazide, Nadolol interactionNattokinaseAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, nattokinase might increase the risk of hypotension when used with antihypertensive drugs.
Read the full Nattokinase + Bendroflumethiazide, Nadolol interactionGinkgo Leaf ExtractSeizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Leaf Extract + Bendroflumethiazide, Nadolol interactionCarbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine TannateQuadratuss, Ry Tuss, Rynatuss, Tri Tannate Plus
How Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interacts with CogniFactors — through 7 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Ephedrine +1 Major
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Leaf Extract + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionHuperzine AAnticholinergic Drugs Moderate
Interaction Summary
Theoretically, huperzine A might decrease the effects of anticholinergic drugs.
Read the full Huperzine A + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionBacopa Leaf ExtractAnticholinergic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concurrent use might decrease the effectiveness of both agents.
Read the full Bacopa Leaf Extract + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionN-acetyl-l-carnitineSerotonergic Drugs Moderate
Interaction Summary
Theoretically, acetyl-L-carnitine might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders, when taken with serotonergic drugs.
Read the full N-acetyl-l-carnitine + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionPhosphatidylserineAnticholinergic Drugs Moderate
Interaction Summary
Theoretically, phosphatidylserine might decrease the effectiveness anticholinergic drugs.
Read the full Phosphatidylserine + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionGinkgo Leaf ExtractSeizure Threshold Lowering Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Leaf Extract + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionDimethylaminoethanol BitartrateAnticholinergic Drugs Minor
Interaction Summary
Theoretically, deanol might decrease the effectiveness of anticholinergic drugs.
Read the full Dimethylaminoethanol Bitartrate + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionDyphylline, Ephedrine, Guaifenesin, PhenobarbitalLufyllin-EPG
How Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interacts with CogniFactors — through 1 ingredient. Tap an ingredient for the detail:
Green Tea Leaf ExtractPhenobarbital (luminal), Ephedrine +1 Major
Interaction Summary
Theoretically, green tea might reduce the effects of phenobarbital and increase the risk for convulsions.
Read the full Green Tea Leaf Extract + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionEphedrine, Guaifenesin (otc Drug)Ephedrine Formula 400, Ephedrine Plus Tabs
How Ephedrine, Guaifenesin (otc Drug) interacts with CogniFactors — through 1 ingredient. Tap an ingredient for the detail:
Green Tea Leaf ExtractStimulant Drugs, Ephedrine Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Leaf Extract + Ephedrine, Guaifenesin (otc Drug) interactionEphedrine, Guaifenesin, Phenobarbital, TheophyllineMudrane GG
How Ephedrine, Guaifenesin, Phenobarbital, Theophylline interacts with CogniFactors — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractPhenobarbital (luminal), Ephedrine +2 Major
Interaction Summary
Theoretically, green tea might reduce the effects of phenobarbital and increase the risk for convulsions.
Read the full Green Tea Leaf Extract + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionGinkgo Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Seizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Leaf Extract + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionBacopa Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Leaf Extract + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionEphedrine, Hydroxyzine, TheophyllineAmi Rax, Marax
How Ephedrine, Hydroxyzine, Theophylline interacts with CogniFactors — through 6 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractStimulant Drugs, Theophylline +1 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Leaf Extract + Ephedrine, Hydroxyzine, Theophylline interactionBacopa Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Anticholinergic Drugs Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Leaf Extract + Ephedrine, Hydroxyzine, Theophylline interactionPhosphatidylserineAnticholinergic Drugs Moderate
Interaction Summary
Theoretically, phosphatidylserine might decrease the effectiveness anticholinergic drugs.
Read the full Phosphatidylserine + Ephedrine, Hydroxyzine, Theophylline interactionHuperzine AAnticholinergic Drugs Moderate
Interaction Summary
Theoretically, huperzine A might decrease the effects of anticholinergic drugs.
Read the full Huperzine A + Ephedrine, Hydroxyzine, Theophylline interactionGinkgo Leaf ExtractSeizure Threshold Lowering Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Leaf Extract + Ephedrine, Hydroxyzine, Theophylline interactionDimethylaminoethanol BitartrateAnticholinergic Drugs Minor
Interaction Summary
Theoretically, deanol might decrease the effectiveness of anticholinergic drugs.
Read the full Dimethylaminoethanol Bitartrate + Ephedrine, Hydroxyzine, Theophylline interactionEphedrine, Phenobarbital, Potassium Iodide, TheophyllineMudrane, Quadrinal
How Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interacts with CogniFactors — through 2 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractPhenobarbital (luminal), Ephedrine +2 Major
Interaction Summary
Theoretically, green tea might reduce the effects of phenobarbital and increase the risk for convulsions.
Read the full Green Tea Leaf Extract + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionGinkgo Leaf ExtractSeizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Leaf Extract + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionEphedrine, Phenobarbital, TheophyllineTedral
How Ephedrine, Phenobarbital, Theophylline interacts with CogniFactors — through 2 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractStimulant Drugs, Theophylline +2 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Leaf Extract + Ephedrine, Phenobarbital, Theophylline interactionGinkgo Leaf ExtractSeizure Threshold Lowering Drugs, Anticonvulsants Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Leaf Extract + Ephedrine, Phenobarbital, Theophylline interactionEzetimibe, AtorvastatinLiptruzet
How Ezetimibe, Atorvastatin interacts with CogniFactors — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractOrganic Anion-transporting Polypeptide Substrates (oatp), Cytochrome P450 3a4 (cyp3a4) Substrates +2 Major
Interaction Summary
Theoretically, green tea might reduce the absorption of organic anion-transporting polypeptide (OATP) substrates.
Read the full Green Tea Leaf Extract + Ezetimibe, Atorvastatin interactionGinkgo Leaf ExtractAtorvastatin (lipitor), Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease the levels and clinical effects of atorvastatin.
Read the full Ginkgo Leaf Extract + Ezetimibe, Atorvastatin interactionBacopa Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP3A4 substrates.
Read the full Bacopa Leaf Extract + Ezetimibe, Atorvastatin interactionNadololCorgard, Nadolol
How Nadolol interacts with CogniFactors — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractNadolol (corgard) Major
Interaction Summary
Green tea seems to reduce the levels and clinical effects of nadolol.
Read the full Green Tea Leaf Extract + Nadolol interactionNattokinaseAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, nattokinase might increase the risk of hypotension when used with antihypertensive drugs.
Read the full Nattokinase + Nadolol interactionGinkgo Leaf ExtractSeizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Leaf Extract + Nadolol interactionTalinololTalinolol
How Talinolol interacts with CogniFactors — through 2 ingredients. Tap an ingredient for the detail:
Ginkgo Leaf ExtractTalinolol Major
Interaction Summary
Taking ginkgo with talinolol seems to increase blood levels of talinolol.
Read the full Ginkgo Leaf Extract + Talinolol interactionNattokinaseAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, nattokinase might increase the risk of hypotension when used with antihypertensive drugs.
Read the full Nattokinase + Talinolol interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with CogniFactors — through 1 ingredient. Tap an ingredient for the detail:
Green Tea Leaf ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with CogniFactors — through 3 ingredients. Tap an ingredient for the detail:
Bacopa Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP3A4 substrates.
Read the full Bacopa Leaf Extract + Ado-trastuzumab Emtansine interactionGinkgo Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Leaf Extract + Ado-trastuzumab Emtansine interactionGreen Tea Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Leaf Extract + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with CogniFactors — through 1 ingredient. Tap an ingredient for the detail:
Green Tea Leaf ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with CogniFactors — through 1 ingredient. Tap an ingredient for the detail:
Green Tea Leaf ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Abacavir, Lamivudine interactionAbametapirXeglyze
How Abametapir interacts with CogniFactors — through 1 ingredient. Tap an ingredient for the detail:
Green Tea Leaf ExtractCytochrome P450 1a2 (cyp1a2) Inhibitors Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Read the full Green Tea Leaf Extract + Abametapir interactionAbciximabReoPro
How Abciximab interacts with CogniFactors — through 4 ingredients. Tap an ingredient for the detail:
R-alpha-lipoic AcidAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full R-alpha-lipoic Acid + Abciximab interactionNattokinaseAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Nattokinase might increase the risk of bleeding when used with anticoagulant/antiplatelet drugs.
Read the full Nattokinase + Abciximab interactionGreen Tea Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea Leaf Extract + Abciximab interactionGinkgo Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin.
Read the full Ginkgo Leaf Extract + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with CogniFactors — through 3 ingredients. Tap an ingredient for the detail:
Bacopa Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP3A4 substrates.
Read the full Bacopa Leaf Extract + Abemaciclib interactionGinkgo Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Leaf Extract + Abemaciclib interactionGreen Tea Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Leaf Extract + Abemaciclib interactionAbiraterone
How Abiraterone interacts with CogniFactors — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Inhibitors +1 Moderate
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Leaf Extract + Abiraterone interactionBacopa Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP3A4 substrates.
Read the full Bacopa Leaf Extract + Abiraterone interactionGinkgo Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Leaf Extract + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with CogniFactors — through 3 ingredients. Tap an ingredient for the detail:
Ginkgo Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Leaf Extract + Abiraterone Acetate interactionBacopa Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP3A4 substrates.
Read the full Bacopa Leaf Extract + Abiraterone Acetate interactionGreen Tea Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Leaf Extract + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with CogniFactors — through 5 ingredients. Tap an ingredient for the detail:
R-alpha-lipoic AcidAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full R-alpha-lipoic Acid + Abrocitinib interactionBacopa Leaf ExtractCytochrome P450 2c9 (cyp2c9) Substrates, Cytochrome P450 2c19 (cyp2c19) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP2C9 substrates.
Read the full Bacopa Leaf Extract + Abrocitinib interactionGinkgo Leaf ExtractAnticoagulant/antiplatelet Drugs, Cytochrome P450 2c19 (cyp2c19) Substrates +1 Moderate
Interaction Summary
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin.
Read the full Ginkgo Leaf Extract + Abrocitinib interactionNattokinaseAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Nattokinase might increase the risk of bleeding when used with anticoagulant/antiplatelet drugs.
Read the full Nattokinase + Abrocitinib interactionGreen Tea Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea Leaf Extract + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with CogniFactors — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Leaf Extract + Acalabrutinib interactionGinkgo Leaf ExtractP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, taking ginkgo with P-glycoprotein substrates might increase the levels and adverse effects of these substrates.
Read the full Ginkgo Leaf Extract + Acalabrutinib interactionBacopa Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP3A4 substrates.
Read the full Bacopa Leaf Extract + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with CogniFactors — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractAntidiabetes Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking green tea with antidiabetes drugs might interfere with blood glucose control.
Read the full Green Tea Leaf Extract + Acarbose interactionGinkgo Leaf ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking ginkgo with antidiabetes drugs might alter the response to antidiabetes drugs.
Read the full Ginkgo Leaf Extract + Acarbose interactionR-alpha-lipoic AcidAntidiabetes Drugs Minor
Interaction Summary
Theoretically, taking alpha-lipoic acid with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full R-alpha-lipoic Acid + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with CogniFactors — through 2 ingredients. Tap an ingredient for the detail:
NattokinaseAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, nattokinase might increase the risk of hypotension when used with antihypertensive drugs.
Read the full Nattokinase + Acebutolol interactionGreen Tea Leaf ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with CogniFactors — through 5 ingredients. Tap an ingredient for the detail:
N-acetyl-l-carnitineAcenocoumarol (sintrom) Moderate
Interaction Summary
Theoretically, acetyl-L-carnitine might increase the anticoagulant effects of acenocoumarol.
Read the full N-acetyl-l-carnitine + Acenocoumarol interactionR-alpha-lipoic AcidAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full R-alpha-lipoic Acid + Acenocoumarol interactionGinkgo Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin.
Read the full Ginkgo Leaf Extract + Acenocoumarol interactionGreen Tea Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea Leaf Extract + Acenocoumarol interactionNattokinaseAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Nattokinase might increase the risk of bleeding when used with anticoagulant/antiplatelet drugs.
Read the full Nattokinase + Acenocoumarol interactionAcepromazineAtravet
How Acepromazine interacts with CogniFactors — through 5 ingredients. Tap an ingredient for the detail:
PhosphatidylserineAnticholinergic Drugs Moderate
Interaction Summary
Theoretically, phosphatidylserine might decrease the effectiveness anticholinergic drugs.
Read the full Phosphatidylserine + Acepromazine interactionBacopa Leaf ExtractAnticholinergic Drugs Moderate
Interaction Summary
Theoretically, concurrent use might decrease the effectiveness of both agents.
Read the full Bacopa Leaf Extract + Acepromazine interactionHuperzine AAnticholinergic Drugs Moderate
Interaction Summary
Theoretically, huperzine A might decrease the effects of anticholinergic drugs.
Read the full Huperzine A + Acepromazine interactionGreen Tea Leaf ExtractPhenothiazines Minor
Interaction Summary
Theoretically, phenothiazines might increase the levels and adverse effects of caffeine.
Read the full Green Tea Leaf Extract + Acepromazine interactionDimethylaminoethanol BitartrateAnticholinergic Drugs Minor
Interaction Summary
Theoretically, deanol might decrease the effectiveness of anticholinergic drugs.
Read the full Dimethylaminoethanol Bitartrate + Acepromazine interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with CogniFactors — through 3 ingredients. Tap an ingredient for the detail:
Bacopa Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Leaf Extract + Acetaminophen interactionGinkgo Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Leaf Extract + Acetaminophen interactionGreen Tea Leaf ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Acetaminophen interactionEach ingredient & the kinds of drugs it affects
For each ingredient in CogniFactors with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Green Tea Leaf Extract
Atorvastatin (Lipitor)
Green tea extract seems to reduce the levels and clinical effects of atorvastatin.
In healthy humans, taking green tea extract 300 mg or 600 mg along with atorvastatin reduces plasma levels of atorvastatin by approximately 24%. The elimination of atorvastatin is not affected. Atorvastatin is a substrate of organic anion-transporting polypeptides (OATPs). Research shows that two of the major catechins found in green tea, epicatechin gallate (ECG) and epigallocatechin gallate (EGCG), inhibit OATPs. Some OATPs are expressed in the small intestine and are responsible for the uptake of drugs and other compounds, which may have resulted in reduced plasma levels of atorvastatin. It is not clear if drinking green tea alters the absorption of atorvastatin.
Ephedrine
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Green tea contains caffeine. There is evidence that using ephedrine with caffeine might increase the risk of serious life-threatening or debilitating adverse effects such as hypertension, myocardial infarction, stroke, seizures, and death.
Nadolol (Corgard)
Green tea seems to reduce the levels and clinical effects of nadolol.
Preliminary clinical research shows that green tea consumption reduces plasma concentrations of nadolol. Compared to a control group, both peak levels and total drug exposure (AUC) of nadolol were reduced by approximately 85% in subjects who drank green tea daily for two weeks. Drinking green tea with nadolol also significantly reduced nadolol's systolic blood pressure lowering effect. Other clinical research shows that a single dose of green tea can affect plasma nadolol levels for at least one hour. Green tea catechins have been shown to inhibit organic anion transporting polypeptides (OATP), one of which, OATP1A2, is involved in the uptake of nadolol in the intestine The interaction is thought to be due primarily to the epigallocatechin gallate (EGCG) content of green tea.
5-Fluorouracil
Theoretically, high doses of green tea might increase the effects and side effects of 5-fluorouracil.
Animal research shows that taking green tea in amounts equivalent to about 6 cups daily in humans for 4 weeks prior to receiving a single injection of 5-fluorouracil increases the maximum plasma levels of 5-fluorouracil by about 2.5-fold and the area under the curve by 425%.
Adenosine (Adenocard)
Theoretically, green tea might decrease the vasodilatory effects of adenosine and interfere with its use prior to stress testing.
Green tea contains caffeine. Caffeine is a competitive inhibitor of adenosine at the cellular level. However, caffeine doesn't seem to affect supplemental adenosine because high interstitial levels of adenosine overcome the antagonistic effects of caffeine. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. However, methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Anticoagulant/Antiplatelet Drugs
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Conflicting reports exist regarding the effect of green tea on bleeding risk when used with anticoagulant or antiplatelet drugs; however, most evidence suggests that drinking green tea in moderate amounts is unlikely to cause a significant interaction. Green tea contains small amounts of vitamin K, approximately 7 mcg per cup. Some case reports have associated the antagonism of warfarin with the vitamin K content of green tea. However, these reports are rare, and very large doses of green tea (about 8-16 cups daily) appear to be needed to cause these effects. Furthermore, the catechins and caffeine in green tea are reported to have antiplatelet activity.
Beta-Adrenergic Agonists
Green tea contains caffeine. Theoretically, concomitant use of large amounts of caffeine might increase cardiac inotropic effects of beta-agonists.
Bortezomib (Velcade)
Theoretically, green tea might interfere with the effects of bortezomib.
In vitro research shows that green tea polyphenols, such as epigallocatechin gallate (EGCG), interact with bortezomib and block its proteasome inhibitory action. This prevents the induction of cell death in multiple myeloma or glioblastoma cancer cell lines. Advise patients taking bortezomib, not to take green tea.
Carbamazepine (Tegretol)
Theoretically, green tea might reduce the effects of carbamazepine and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that taking caffeine can lower the anticonvulsant effects of carbamazepine and can induce seizures when taken in doses above 400 mg/kg. Human research has shown that taking caffeine 300 mg in three divided doses along with carbamazepine 200 mg reduces the bioavailability of carbamazepine by 32% and prolongs the plasma half-life of carbamazepine 2-fold in healthy individuals.
Celiprolol (Celicard)
Theoretically, green tea might reduce the levels and clinical effects of celiprolol.
In a small human study, taking green tea daily for 4 days appears to decrease blood and urine levels of celiprolol by at least 98%. This interaction is possibly due to the inhibition of organic anion transporting polypeptide (OATP). Green tea catechins have been shown to inhibit organic anion transporting polypeptides (OATP), one of which, OATP1A2, is found in the intestine The interaction is thought to be due primarily to the epigallocatechin gallate (EGCG) content of green tea.
Cimetidine (Tagamet)
Theoretically, concomitant use might increase the effects and adverse effects of caffeine in green tea.
Green tea contains caffeine. Cimetidine can reduce caffeine clearance by 31% to 42%.
Clozapine (Clozaril)
Theoretically, green tea might increase the levels and adverse effects of clozapine and acutely exacerbate psychotic symptoms.
Animal research suggests that, although green tea extract does not affect the elimination of clozapine, it delays the time to reach peak concentration and reduces the peak plasma levels. Also, concomitant administration of green tea and clozapine might theoretically cause acute exacerbation of psychotic symptoms due to the caffeine in green tea. Caffeine can increase the effects and toxicity of clozapine. Caffeine doses of 400-1000 mg daily inhibit clozapine metabolism. Clozapine is metabolized by cytochrome P450 1A2 (CYP1A2). Researchers speculate that caffeine might inhibit CYP1A2. However, there is no reliable evidence that caffeine affects CYP1A2. There is also speculation that genetic factors might make some patients be more sensitive to the interaction between clozapine and caffeine.
Contraceptive Drugs
Theoretically, concomitant use might increase the effects and adverse effects of caffeine found in green tea.
Green tea contains caffeine. Oral contraceptives can decrease caffeine clearance by 40% to 65%.
Cytochrome P450 1A2 (Cyp1A2) Inhibitors
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Caffeine is metabolized by cytochrome P450 1A2 (CYP1A2),. Theoretically, drugs that inhibit CYP1A2 may decrease the clearance rate of caffeine from green tea and increase caffeine levels.
Dipyridamole (Persantine)
Theoretically, green tea might decrease the vasodilatory effects of dipyridamole and interfere with its use prior to stress testing.
Green tea contains caffeine. Caffeine might inhibit dipyridamole-induced vasodilation. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. Methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Disulfiram (Antabuse)
Theoretically, disulfiram might increase the risk of adverse effects from caffeine.
In human research, disulfiram decreases the clearance and increases the half-life of caffeine.
Diuretic Drugs
Theoretically, using green tea with diuretic drugs might increase the risk of hypokalemia.
Green tea contains caffeine. In excessive amounts, caffeine can reduce potassium levels due to stimulation of the sodium-potassium pump. Diuretics can also cause lower potassium levels.
Estrogens
Theoretically, estrogens might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Estrogen inhibits caffeine metabolism.
Ethosuximide (Zarontin)
Theoretically, green tea might reduce the effects of ethosuximide and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that caffeine 92.4 mg/kg can decrease the anticonvulsant activity of ethosuximide. However, this effect has not been reported in humans.
Felbamate (Felbatol)
Theoretically, green tea might reduce the effects of felbamate and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that a high dose of caffeine 161.7 mg/kg can decreases the anticonvulsant activity of felbamate. However, this effect has not been reported in humans.
Fexofenadine (Allegra)
Green tea can decrease blood levels of fexofenadine.
Clinical research shows that green tea can significantly decrease blood levels and excretion of fexofenadine. Taking green tea extract with a dose of fexofenadine decreased bioavailability of fexofenadine by about 30%. In vitro, green tea inhibits the cellular accumulation of fexofenadine by inhibiting the organic anion transporting polypeptide (OATP) drug transporter. Research shows that two of the major catechins found in green tea, epicatechin gallate (ECG) and epigallocatechin gallate (EGCG), inhibit OATPs, specifically OATP1A2, OATP1B1, and OATP2B1. In addition, green tea has been shown to reduce the absorption of some drugs that are OATP substrates.
Flutamide (Eulexin)
Theoretically, green tea might increase the levels and adverse effects of flutamide.
Green tea contains caffeine. In vitro evidence suggests that caffeine can inhibit the metabolism of flutamide. Theoretically, concomitant use of caffeine and flutamide might increase serum concentrations of flutamide and increase the risk adverse effects.
Fluvoxamine (Luvox)
Theoretically, fluvoxamine might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Fluvoxamine reduces caffeine metabolism.
Hepatotoxic Drugs
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Green tea extract supplements have been linked to several cases of hepatotoxicity and might have additive hepatotoxic effects with other drugs..
Imatinib (Gleevec)
Theoretically, green tea might reduce the levels and clinical effects of imatinib.
In animal research, a single dose of green tea extract reduces the area under the curve (AUC) of imatinib by up to approximately 64% and its main metabolite N-desmethyl imatinib by up to approximately 81%. This interaction has not been shown in humans. The mechanism of action is unclear but may involve multiple pathways.
Ginkgo Leaf Extract
Talinolol
Taking ginkgo with talinolol seems to increase blood levels of talinolol.
There is some evidence that using ginkgo leaf extract 120 mg orally three times daily for 14 days can increase levels of talinolol by 36% in healthy male individuals. However, single doses of ginkgo do not seem to affect talinolol pharmacokinetics.
Alprazolam (Xanax)
Theoretically, ginkgo might decrease the levels and clinical effects of alprazolam.
In clinical research, ginkgo extract (Ginkgold) 120 mg twice daily seems to decrease alprazolam levels by about 17%. However, ginkgo does not appear to decrease the elimination half-life of alprazolam. This suggests that ginkgo is more likely to decrease absorption of alprazolam rather than induce hepatic metabolism of alprazolam.
Anticoagulant/Antiplatelet Drugs
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin. Theoretically, ginkgo might increase the risk of bleeding if used with other anticoagulant or antiplatelet drugs.
Several pharmacodynamic studies suggest that ginkgo inhibits platelet aggregation. It is thought that the ginkgo constituent, ginkgolide B, displaces platelet-activating factor (PAF) from its binding sites, decreasing blood coagulation. Several case reports have documented serious bleeding events in patients taking ginkgo. However, population and clinical studies have produced mixed results. Some evidence shows that short-term use of ginkgo leaf does not significantly reduce platelet aggregation and blood clotting. A study in healthy males who took a specific ginkgo leaf extract (EGb 761) 160 mg twice daily for 7 days found no change in prothrombin time. An analysis of a large medical record database suggests that ginkgo increases the risk of a bleeding adverse event by 38% when taken concurrently with warfarin. It has been suggested that ginkgo has to be taken for at least 2-3 weeks to have a significant effect on platelet aggregation. However, a meta-analysis of 18 studies using standardized ginkgo extracts, 80-480 mg daily for up to 32 weeks, did not find a significant effect on platelet aggregation, fibrinogen concentration, or PT/aPTT. In addition, a single dose of ginkgo plus clopidogrel or ticlopidine does not seem to significantly increase bleeding time or platelet aggregation. Also, taking ginkgo leaf extract daily for 8 days in conjunction with rivaroxaban does not affect anti-factor Xa activity; however, this study did not evaluate bleeding time.
Anticonvulsants
Theoretically, ginkgo might reduce the effectiveness of anticonvulsants.
Ginkgo seeds contain ginkgotoxin. Large amounts of ginkgotoxin can cause neurotoxicity and seizure. Ginkgotoxin is present in much larger amounts in ginkgo seeds than leaves. Ginkgo leaf extract contains trace amounts of ginkgotoxin. The amount of ginkgotoxin in ginkgo leaf and leaf extract seems unlikely to cause toxicity. However, there are anecdotal reports of seizure occurring after use of ginkgo leaf both in patients without a history of seizure disorder and in those with previously well-controlled epilepsy.
Antidiabetes Drugs
Theoretically, taking ginkgo with antidiabetes drugs might alter the response to antidiabetes drugs.
Ginkgo leaf extract seems to alter insulin secretion and metabolism, and might affect blood glucose levels in people with type 2 diabetes. The effect of ginkgo seems to differ depending on the insulin and treatment status of the patient. In diet-controlled diabetes patients with hyperinsulinemia, taking ginkgo does not seem to significantly affect insulin or blood glucose levels. In patients with hyperinsulinemia who are treated with oral hypoglycemic agents, taking ginkgo seems to decrease insulin levels and increase blood glucose following an oral glucose tolerance test. Researchers speculate that this could be due to ginkgo-enhanced hepatic metabolism of insulin. In patients with pancreatic exhaustion, taking ginkgo seems to stimulate pancreatic beta-cells, resulting in increased insulin and C-peptide levels, but with no significant change in blood glucose levels in response to an oral glucose tolerance test.
Atorvastatin (Lipitor)
Theoretically, ginkgo might decrease the levels and clinical effects of atorvastatin.
In humans, intake of ginkgo extract appears to increase atorvastatin clearance, reducing the area under the curve of atorvastatin by 10% to 14% and the maximum concentration by 29%. However, this interaction does not appear to affect cholesterol synthesis and absorption. Further, a model in rats with hyperlipidemia suggests that administering ginkgo extract does not impact blood levels of atorvastatin and leads to lower total cholesterol, low-density lipoprotein cholesterol, and triglycerides when compared with rats given atorvastatin alone.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Laboratory research suggests that ginkgo leaf extract can mildly inhibit CYP1A2 enzymes. However, clinical research suggests ginkgo might not affect CYP1A2. Until more is known, use ginkgo cautiously in patients taking drugs metabolized by these enzymes.
Cytochrome P450 2C19 (Cyp2C19) Substrates
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP2C19.
Some clinical research shows that a specific ginkgo leaf extract (Remembrance, Herbs Product LTD) 140 mg twice daily can induce CYP2C19 enzymes and potentially decrease levels of drugs metabolized by these enzymes. However, other clinical research shows that taking ginkgo 120 mg twice daily for 12 days has no effect on levels of drugs metabolized by CYP2C19.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, ginkgo might increase levels of drugs metabolized by CYP2C9.
In vitro, a specific standardized extract of ginkgo leaf (EGb 761) inhibits CYP2C9 activity . The terpenoid (ginkgolides) and flavonoid (quercetin, kaempferol, etc.) constituents seem to be responsible for this effect. Most ginkgo extracts contain some amount of these constituents. Therefore, other ginkgo leaf extracts might also inhibit the CYP2C9 enzyme. However, clinical research suggests that ginkgo might not have a significant effect on CYP2C9 in humans. Ginkgo does not seem to significantly affect the pharmacokinetics of CYP2C9 substrates diclofenac or tolbutamide.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
There is conflicting evidence about whether ginkgo induces or inhibits CYP3A4. Ginkgo does not appear to affect hepatic CYP3A4. However, it is not known if ginkgo affects intestinal CYP3A4. Preliminary clinical research suggests that taking ginkgo does not significantly affect levels of donepezil, lopinavir, or ritonavir, which are all CYP3A4 substrates. Other clinical research also suggests ginkgo does not significantly affect CYP3A4 activity. However, there are two case reports of decreased efavirenz concentrations and increased viral load in patients taking ginkgo. It is suspected that terpenoids from the ginkgo extract reduced drug levels by inducing cytochrome P450 3A4 (CYP3A4).
Efavirenz (Sustiva)
Theoretically, ginkgo might decrease the levels and clinical effects of efavirenz.
There are two case reports of decreased efavirenz concentrations and increased viral load in patients taking ginkgo. In one case, an HIV-positive male experienced over a 50% decrease in efavirenz levels over the course of 14 months while taking ginkgo extract. HIV-1 RNA copies also increased substantially, from less than 50 to more than 1500. It is suspected that terpenoids from the ginkgo extract reduced drug levels by inducing cytochrome P450 3A4 (CYP3A4). In another case report, a patient stable on antiviral therapy including efavirenz for 10 years, had an increase in viral load from <50 copies/mL to 1350 copies/mL after 2 months of taking a combination of supplements including ginkgo. After stopping ginkgo, the viral load was again controlled with the same antiviral therapy regimen.
Ibuprofen (Advil, Others)
Theoretically, ginkgo might increase the risk of bleeding when used with ibuprofen.
Ginkgo might have antiplatelet effects and has been associated with several case reports of spontaneous bleeding. In one case, a 71-year-old male had taken a specific ginkgo extract (Gingium, Biocur) 40 mg twice daily for 2.5 years. About 4 weeks after starting ibuprofen 600 mg daily he experienced a fatal intracerebral hemorrhage. However, the antiplatelet effects of ginkgo have been questioned. A meta-analysis and other studies have not found a significant antiplatelet effect with standardized ginkgo extracts, 80 mg to 480 mg taken daily for up to 32 weeks.
P-Glycoprotein Substrates
Theoretically, taking ginkgo with P-glycoprotein substrates might increase the levels and adverse effects of these substrates.
A small clinical study in healthy volunteers shows that using ginkgo leaf extract 120 mg orally three times daily for 14 days can increase levels of the P-glycoprotein substrate, talinolol, by 36% in healthy male individuals. However, single doses of ginkgo do not have the same effect.
Risperidone (Risperdal)
Theoretically, taking ginkgo with risperidone might increase the levels and adverse effects of risperidone.
A single case of priapism has been reported for a 26-year-old male with schizophrenia who used risperidone 3 mg daily along with ginkgo extract 160 mg daily. Risperidone is metabolized by cytochrome P450 (CYP) 2D6 and CYP3A4. CYP3A4 activity might be affected by ginkgo. Theoretically, ginkgo may inhibit the metabolism of risperidone and increase the risk of adverse effects.
Rosiglitazone (Avandia)
Theoretically, ginkgo might decrease the levels and clinical effects of rosiglitazone.
Animal research shows that ginkgo leaf extract orally 100 or 200 mg/kg daily for 10 days alters the pharmacodynamics of rosiglitazone in a dose-dependent manner. The 100 mg/kg and 200 mg/kg doses reduce the area under the concentration time curve (AUC) of rosiglitazone by 39% and 52%, respectively, and the half-life by 28% and 39%, respectively. It is hypothesized that these changes may be due to induction of cytochrome P450 2C8 by ginkgo.
Seizure Threshold Lowering Drugs
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Ginkgo seeds contain ginkgotoxin. Large amounts of ginkgotoxin can cause neurotoxicity and seizure. Ginkgotoxin is present in much larger amounts in ginkgo seeds than leaves. Ginkgo leaf extract contains trace amounts of ginkgotoxin. The amount of ginkgotoxin in ginkgo leaf and leaf extract seems unlikely to cause toxicity. However, there are anecdotal reports of seizure occurring after use of ginkgo leaf both in patients without a history of seizure disorder and in those with previously well-controlled epilepsy.
Simvastatin (Zocor)
Theoretically, ginkgo might decrease the levels and clinical effects of simvastatin.
Clinical research shows that taking ginkgo extract can reduce the area under the curve and maximum concentration of simvastatin by 32% to 39%. However, ginkgo extract does not seem to affect the cholesterol-lowering ability of simvastatin.
Sofosbuvir (Sovaldi)
Theoretically, ginkgo might increase the levels and clinical effects of sofosbuvir.
Animal research in rats shows that giving a ginkgo extract 25 mg/kg orally daily for 14 days increases the area under the concentration time curve (AUC) after a single sofosbuvir dose of 40 mg/kg by 11%, increases the half-life by 60%, and increases the plasma concentration at 4 hours by 38%. This interaction appears to be related to the inhibition of intestinal P-glycoprotein by ginkgo.
Tacrolimus (Prograf)
Theoretically, ginkgo might increase the blood levels of tacrolimus.
In vitro evidence suggests that certain biflavonoids in ginkgo leaves (i.e. amentoflavone, ginkgetin, bilobetin) may inhibit the metabolism of tacrolimus by up to 50%. This interaction appears to be time-dependent and due to inhibition of cytochrome P450 (CYP) 3A4 by these bioflavonoids. In rats given tacrolimus 1 mg/kg orally, amentoflavone was shown to increase the area under the concentration time curve (AUC) of tacrolimus by 3.8-fold.
Trazodone (Desyrel)
Theoretically, ginkgo might increase the levels and clinical effects of trazodone.
In a case report, an Alzheimer patient taking trazodone 20 mg twice daily and ginkgo leaf extract 80 mg twice daily for four doses became comatose. The coma was reversed by administration of flumazenil (Romazicon). Coma might have been induced by excessive GABA-ergic activity. Ginkgo flavonoids are thought to have GABA-ergic activity and act directly on benzodiazepine receptors. Ginkgo might also increase metabolism of trazodone to active GABA-ergic metabolites, possibly by inducing cytochrome P450 3A4 (CYP3A4) metabolism.
Warfarin (Coumadin)
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin.
Several pharmacodynamic studies suggest that ginkgo inhibits platelet aggregation. It is thought that the ginkgo constituent, ginkgolide B, displaces platelet-activating factor (PAF) from its binding sites, decreasing blood coagulation. Several case reports have documented serious bleeding events in patients taking ginkgo. Information from a medical database suggests that when taken concurrently with warfarin, ginkgo increases the risk of a bleeding adverse event by 38%. There is also some evidence that ginkgo leaf extract can inhibit cytochrome P450 2C9, an enzyme that metabolizes warfarin. This could result in increased warfarin levels. However, population and clinical research has produced mixed results. Clinical research in healthy people suggests that ginkgo has no effect on INR, or the pharmacokinetics or pharmacodynamics of warfarin. A meta-analysis of 18 studies using standardized ginkgo extracts, 80 mg to 480 mg daily for up to 32 weeks, did not find a significant effect on platelet aggregation, fibrinogen concentration, or PT/aPTT. There is also some preliminary clinical research that suggests ginkgo might not significantly increase the effects of warfarin in patients that have a stable INR.
Nifedipine (Procardia)
Theoretically, taking ginkgo with oral, but not intravenous, nifedipine might increase levels and adverse effects of nifedipine.
Animal research and some clinical evidence suggests that taking ginkgo leaf extract orally in combination with oral nifedipine might increase nifedipine levels and cause increased side effects, such as headaches, dizziness, and hot flushes. However, taking ginkgo orally does not seem to affect the pharmacokinetics of intravenous nifedipine.
Omeprazole (Prilosec)
Theoretically, taking ginkgo with omeprazole might decrease the levels and clinical effects of omeprazole.
Clinical research shows that a specific ginkgo leaf extract (Remembrance, Herbs Product LTD) 140 mg twice daily can induce cytochrome P450 (CYP) 2C19 enzymes and decrease levels of omeprazole by about 27% to 42%.
Bacopa Leaf Extract
Anticholinergic Drugs
Theoretically, concurrent use might decrease the effectiveness of both agents.
Bacopa seems to inhibit acetylcholinesterase and might increase acetylcholine levels, which could counteract the effects of anticholinergic drugs. Similarly, anticholinergic drugs might counteract the cholinergic effects of bacopa.
Cevimeline (Evoxac)
Theoretically, bacopa might increase the effects and adverse effects of cevimeline.
In one case, a 58-year-old female taking cevimeline long-term for Sjogren syndrome experienced hyperhidrosis, malaise, nausea, and tachycardia shortly after taking a single dose of bacopa. Symptoms resolved after two days. Cevimeline is metabolized by cytochrome P450 (CYP) 2D6 and CYP3A4, and researchers theorize that bacopa may have inhibited these isoenzymes. However, it is unclear if bacopa causes clinically significant inhibition of either CYP2D6 or CYP3A4.
Cholinergic Drugs
Theoretically, concurrent use of bacopa with other cholinergic drugs might have additive effects.
Bacopa seems to inhibit acetylcholinesterase and might increase acetylcholine levels. Theoretically, this could result in additive cholinergic effects when used with cholinergic drugs.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Research on the effects of bacopa extracts on CYP1A2 enzymes is conflicting. Some in vitro evidence shows that bacopa extract can moderately and non-competitively inhibit CYP1A2, while other in vitro evidence suggests that any effect is unlikely to be clinically significant.
Cytochrome P450 2C19 (Cyp2C19) Substrates
Theoretically, bacopa might increase the levels and adverse effects of CYP2C19 substrates.
In vitro evidence suggests that bacopa extract can moderately and non-competitively inhibit CYP2C19 enzymes. It is not known whether this is clinically significant.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, bacopa might increase the levels and adverse effects of CYP2C9 substrates.
Research on the effect of bacopa extracts on CYP2C9 enzymes is conflicting. Some in vitro evidence suggests that bacopa extract can moderately and non-competitively inhibit CYP2C9, while other in vitro evidence suggests that any effect is unlikely to be clinically significant.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, bacopa might increase the levels and adverse effects of CYP3A4 substrates.
Research on the effects of bacopa extracts on CYP3A4 enzymes is conflicting. Some in vitro evidence suggests that bacopa extract can moderately and competitively inhibit CYP3A4, while other in vitro evidence suggests that any effect is unlikely to be clinically significant.
Thyroid Hormone
Theoretically, bacopa might have additive effects when used with thyroid hormone.
Animal research suggests that bacopa increases thyroxine (T4) levels in mice by about 40%.
Nattokinase
Anticoagulant/Antiplatelet Drugs
Nattokinase might increase the risk of bleeding when used with anticoagulant/antiplatelet drugs.
Nattokinase has thrombolytic and anticoagulant effects. There is a case report of intracranial hemorrhage in a patient who added nattokinase to aspirin therapy.
Antihypertensive Drugs
Theoretically, nattokinase might increase the risk of hypotension when used with antihypertensive drugs.
Some clinical research suggests that nattokinase may reduce systolic and diastolic blood pressure.
R-Alpha-Lipoic Acid
Alkylating Agents
Theoretically, the antioxidant effects of alpha-lipoic acid might alter the effectiveness of alkylating agents.
The use of antioxidants like alpha-lipoic acid during chemotherapy is controversial. There are concerns that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as alpha-lipoic acid have on chemotherapy. Advise patients to consult their oncologist before using alpha-lipoic acid.
Anticoagulant/Antiplatelet Drugs
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro, alpha-lipoic acid inhibits platelet aggregation.
Antitumor Antibiotics
Theoretically, the antioxidant effects of alpha-lipoic acid might alter the effectiveness of antitumor antibiotics.
The use of antioxidants like alpha-lipoic acid during chemotherapy is controversial. There are concerns that antioxidants could reduce the activity of antitumor antibiotic drugs, which work by generating free radicals. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as alpha-lipoic acid have on chemotherapy involving antitumor antibiotics. Advise patients to consult their oncologist before using alpha-lipoic acid.
Thyroid Hormone
Theoretically, alpha-lipoic acid might decrease the effects of thyroid hormone drugs.
Animal research suggests that co-administration of thyroxine with alpha-lipoic acid reduces conversion into the active T3 form.
Antidiabetes Drugs
Theoretically, taking alpha-lipoic acid with antidiabetes drugs might increase the risk of hypoglycemia.
Although some small clinical studies have suggested that alpha-lipoic acid can lower blood glucose levels, larger clinical studies in patients with diabetes have shown no clinically meaningful effect. Additionally, co-administration of single doses of alpha-lipoic acid and glyburide or acarbose did not cause detectable drug interactions in healthy volunteers.
Dimethylaminoethanol Bitartrate
Anticholinergic Drugs
Theoretically, deanol might decrease the effectiveness of anticholinergic drugs.
Deanol is thought to increase acetylcholine levels.
Cholinergic Drugs
Theoretically, deanol might increase the effects and adverse effects of cholinergic drugs.
Deanol is thought to increase acetylcholine levels.
Phosphatidylserine
Anticholinergic Drugs
Theoretically, phosphatidylserine might decrease the effectiveness anticholinergic drugs.
Phosphatidylserine is thought to increase acetylcholine levels, which could theoretically interfere with the activity of anticholinergic agents.
Cholinergic Drugs
Theoretically, phosphatidylserine might have additive effects with cholinergic drugs.
Phosphatidylserine is thought to increase acetylcholine levels, which could theoretically lead to additive cholinergic effects when used with cholinergic drugs.
Huperzine A
Anticholinergic Drugs
Theoretically, huperzine A might decrease the effects of anticholinergic drugs.
Huperzine A has acetylcholinesterase (AChE) inhibiting effects. In animal models, huperzine A reversed cognitive deficits induced by scopolamine, an anticholinergic drug.
Cholinergic Drugs
Theoretically, concurrent use of huperzine A with cholinergic drugs might increase the effects and side effects of these medications.
Huperzine A can inhibit acetylcholinesterase (AChE) and might cause cumulative effects if used with cholinergic drugs.
N-Acetyl-L-Carnitine
Acenocoumarol (Sintrom)
Theoretically, acetyl-L-carnitine might increase the anticoagulant effects of acenocoumarol.
L-carnitine, the parent compound of acetyl-L-carnitine, might enhance the anticoagulant effects of acenocoumarol, an oral anticoagulant that is similar to warfarin, but shorter-acting. There are at least two case reports of INR elevation when L-carnitine was taken with acenocoumarol. In one case, a 33-year-old male with a previously stable INR had an elevated INR of 4.65 after L-carnitine was started and continued for 10 weeks. INR normalized after discontinuation of the L-carnitine-containing product. It is unclear if such an interaction would also occur with acetyl-L-carnitine.
Serotonergic Drugs
Theoretically, acetyl-L-carnitine might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders, when taken with serotonergic drugs.
Animal research shows that acetyl-L-carnitine can increase levels of serotonin in the brain.
Thyroid Hormone
Theoretically, acetyl-L-carnitine might decrease the effectiveness of thyroid hormone replacement.
L-carnitine appears to act as a peripheral thyroid hormone antagonist by inhibiting entry of thyroid hormone into the nucleus of cells. Taking L-carnitine also seems to diminish some of the symptoms of hyperthyroidism. It is unclear if such an interaction would occur with acetyl-L-carnitine.
Warfarin (Coumadin)
Theoretically, acetyl-L-carnitine might increase the anticoagulant effects of warfarin.
L-carnitine, the parent compound of acetyl-L-carnitine, might increase the anticoagulant effects of acenocoumarol, a shorter-acting oral anticoagulant similar to warfarin. There is not enough information to know whether this interaction occurs with acetyl-L-carnitine and warfarin.
Brand information
Manufacturer and brand details for CogniFactors, from the product label.
Nutra BioGenesis
- Name
- Nutra BioGenesis
- City
- Shelburne Falls
- State
- MA
- ZipCode
- 01370
- Phone Number
- 800-538-5888
- Web Address
- www.nutrabiogenesis.com
CogniFactors by Nutra BioGenesis: Common Questions
Does CogniFactors by Nutra BioGenesis interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Does this product actually improve memory or focus?
What are the most common side effects I might notice?
Can I take this while pregnant or breastfeeding?
Will this interfere with my blood pressure or cholesterol medication?
Is there any risk of bleeding with this product?
What is nattokinase, and why is it in a cognitive supplement?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if CogniFactors is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind CogniFactors’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Alpha-lipoic Acid
Interacts with 263 drugsAlpha-lipoic acid (ALA) is an antioxidant made naturally by the body and found in small amounts in foods. It is most studied for diabetic nerve pain, where some evidence suggests it may help...
Read the full Alpha-lipoic Acid monograph → Herb & supplement monographAcetyl-l-carnitine
Interacts with 203 drugsAcetyl-L-carnitine is a form of the amino acid carnitine that the body uses to help produce energy in cells. It is most studied for nerve pain and memory-related conditions, though the evide...
Read the full Acetyl-l-carnitine monograph → Herb & supplement monographDeanol
Interacts with 219 drugsDeanol (DMAE) is a compound related to choline that is marketed for memory, focus, and mood, but solid human evidence for most of these uses is limited or mixed. It can cause side effects in...
Read the full Deanol monograph → Herb & supplement monographNattokinase
Interacts with 289 drugsNattokinase is an enzyme from the fermented soybean food natto that may have mild blood-thinning and blood-flow effects. Some small studies hint at benefits for blood pressure and circulatio...
Read the full Nattokinase monograph → Herb & supplement monographPhosphatidylserine
Interacts with 219 drugsPhosphatidylserine is a natural fat-like compound found in cell membranes, especially in the brain, and it is sold mainly to support memory and thinking. Some research suggests possible bene...
Read the full Phosphatidylserine monograph → Herb & supplement monographGinkgo
Interacts with 1,266 drugsGinkgo is one of the world's most popular herbal supplements, mostly taken to support memory and circulation. The evidence for these uses is mixed and generally weak, and it is not proven to...
Read the full Ginkgo monograph → Herb & supplement monographHuperzine A
Interacts with 219 drugsHuperzine A is a purified compound from a Chinese clubmoss that acts like a mild cholinesterase inhibitor, similar in mechanism to some prescription Alzheimer's drugs. Some small studies sug...
Read the full Huperzine A monograph → Herb & supplement monographGreen Tea
Interacts with 1,293 drugsGreen tea is a popular beverage rich in antioxidants called catechins, and drinking it in normal amounts is considered safe for most people. Concentrated green tea extracts are a different s...
Read the full Green Tea monograph → Herb & supplement monographBacopa
Interacts with 930 drugsBacopa is an Ayurvedic herb most often used for memory and thinking. Some small studies suggest it may modestly help memory when taken regularly for several weeks, but the evidence is limite...
Read the full Bacopa monograph →Sources & How We Checked
CogniFactors's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 444 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Alpha-lipoic Acid 48 references
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Anon. Alpha-lipoic acid. Altern Med Rev 1998;3:308-10.
- Konrad T, Vicini P, Kusterer K, et al. Alpha-lipoic acid treatment decreases serum lactate and pyruvate concentrations and improves glucose effectiveness in lean and obese patients with Type 2 diabetes. Diabetes Care 1999;22:280-7. PubMed
- Ziegler D, Hanefeld M, Ruhnau KJ, et al. Treatment of symptomatic diabetic peripheral neuropathy with the antioxidant alpha-lipoic acid: A 3-week, multicentre randomized controlled trial (ALADIN Study). Diabetologia 1995;38:1425-33.
- Gleiter CH, Schreeb KH, Freudenthaler S, et al. Lack of interaction between thioctic acid, glibenclamide and acarbose. Br J Clin Pharmacol 1999;48:819-25. PubMed
- Jacob S, Henriksen EJ, Tritschler HJ, et al. Improvement of insulin-stimulated glucose-disposal in type 2 diabetes after repeated parenteral administration of thioctic acid. Exp Clin Endocrinol Diabet 1996;104:284-8. PubMed
- Jacob S, Henriksen EJ, Schiemann AL, et al. Enhancement of glucose disposal in patients with type 2 diabetes by alpha-lipoic acid. Arzneimittelforschung 1995;45:872-4.
- Jacob S, Ruus P, Hermann R, et al. Oral administration of RAC-alpha-lipoic acid modulates insulin sensitivity in patients with type-2 diabetes mellitus: a placebo-controlled, pilot trial. Free Rad Biol Med 1999;27:309-14.
- Segermann J, Hotze A, Ulrich H, Rao GS. Effect of alpha-lipoic acid on the peripheral conversion of thyroxine to triiodothyronine and on serum lipid-, protein- and glucose levels. Arzneimittelforschung 1991;41:1294-8.
- Beitner H. Randomized, placebo controlled, double-blind study on the clinical efficacy of a cream containing 5% alpha-lipoic acid related to photoaging of facial skin. Br J Dermatol 2003;149:841-9.
- Ziegler D, Nowak H, Kempler P, et al. Treatment of symptomatic diabetic polyneuropathy with the antioxidant alpha-lipoic acid: A meta-analysis. Diabet Med 2004;21:114-21.
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Vincent HK, Bourguignon CM, Vincent KR, Taylor AG. Effects of alpha-lipoic acid supplementation in peripheral arterial disease: a pilot study. J Alt Complement Med 2007;13:577-84. PubMed
- Furukawa N, Miyamura N, Nishida K, et al. Possible relevance of alpha lipoic acid contained in a health supplement in a case of insulin autoimmune syndrome. Diabetes Res Clin Pract 2007;75:366-7. PubMed
- Ziegler D., Ametov A., Barinov A., Dyck P. J., Gurieva I., Low P. A., Munzel U., Yakhno N., Raz I., Novosadova M., Maus J., Samigullin, R. Oral treatment with alpha-lipoic acid improves symptomatic diabetic polyneuropathy: the SYDNEY 2 trial. Diabetes Car
- Gu X. M., Zhang S. S., Wu J. C., Tang Z. Y., Lu Z. Q., Li H., Liu C., Chen L., Ning, G. [Efficacy and safety of high-dose a-lipoic acid in the treatment of diabetic polyneuropathy]. Zhonghua Yi Xue Za Zhi 2010;90(35):2473-2476.
- Porasuphatana S., Suddee S., Nartnampong A., Konsil J., Harnwong B., Santaweesuk A. Glycemic and oxidative status of patients with type 2 diabetes mellitus following oral administration of alpha-lipoic acid: a randomized double-blinded placebo-controlled
- Ansar H., Mazloom Z., Kazemi F., Hejazi N. Effect of alpha-lipoic acid on blood glucose, insulin resistance and glutathione peroxidase of type 2 diabetic patients. Saudi Med J 2011;32(6):584-588. DOI
- de Oliveira A. M., Rondó P. H., Luzia L. A., D'Abronzo F. H., Illison V. K. The effects of lipoic acid and a-tocopherol supplementation on the lipid profile and insulin sensitivity of patients with type 2 diabetes mellitus: a randomized, double-blind, pla
- Mazloom Z., Ansar H. The Effect of Alpha-Lipoic Acid on Blood Pressure in Type 2 Diabetics. Iranian Journal of Endocrinology and Metabolism 2009;11(3):245-250.
- Volchegorskii I. A., Rassokhina L. M., Koliadich M. I., Alekseev M. I. [Comparative study of alpha-lipoic acid and mexidol effects on affective status, cognitive functions and quality of life in diabetes mellitus patients]. Eksp Klin Farmakol 2011;74(11):
- Cavalcanti D. R., da Silveira F. R. Alpha lipoic acid in burning mouth syndrome--a randomized double-blind placebo-controlled trial. J Oral Pathol Med 2009;38(3):254-261. PubMed
- Koh E. H., Lee W. J., Lee S. A., Kim E. H., Cho E. H., Jeong E., Kim D. W., Kim M. S., Park J. Y., Park K. G., Lee H. J., Lee I. K., Lim S., Jang H. C., Lee K. H., Lee K. U. Effects of alpha-lipoic Acid on body weight in obese subjects. Am J Med 2011;124( PubMed
- Bergqvist-Karlsson, A., Thelin, I., and Bergendorff, O. Contact dermatitis to alpha-lipoic acid in an anti-wrinkle cream. Contact Dermatitis 2006;55(1):56-57.
- Tang, J., Wingerchuk, D. M., Crum, B. A., Rubin, D. I., and Demaerschalk, B. M. Alpha-lipoic acid may improve symptomatic diabetic polyneuropathy. Neurologist. 2007;13(3):164-167. PubMed
- Hegazy SK, Tolba OA, Mostafa TM, Eid MA, El-Afify DR. Alpha-lipoic acid improves subclinical left ventricular dysfunction in asymptomatic patients with type 1 diabetes. Rev Diabet Stud 2013;10(1):58-67. PubMed
- Huang Z, Wan X, Liu J, et al. Short-term continuous subcutaneous insulin infusion combined with insulin sensitizers rosiglitazone, metformin, or antioxidant a-lipoic acid in patients with newly diagnosed type 2 diabetes mellitus. Diabetes Technol Ther 201
- Sarezky D, Raquib AR, Dunaief JL, Kim BJ. Tolerability in the elderly population of high-dose alpha lipoic acid: a potential antioxidant therapy for the eye. Clin Ophthalmol. 2016 Sep 29;10:1899-1903. PubMed
- Boriani F, Granchi D, Roatti G, Merlini L, Sabattini T, Baldini N. Alpha-lipoic acid after median nerve decompression at the carpal tunnel: a randomized controlled trial. J Hand Surg Am. 2017 Apr;42(4):236-42. PubMed
- Karkabounas S, Papadopoulos N, Anastasiadou C, et al. Effects of a-lipoic Acid, carnosine, and thiamine supplementation in obese patients with type 2 diabetes mellitus: A randomized, double-blind study. J Med Food. 2018;21(12):1197-1203.
- Murray GL, Colombo J. (r)Alpha lipoic acid is a safe, effective pharmacologic therapy of chronic orthostatic hypotension associated with low sympathetic tone. Int J Angiol. 2019;28(3):188-193. PubMed
- Bobe G, Michels AJ, Zhang WJ, et al. A randomized controlled trial of long-term (R)-α-lipoic acid supplementation promotes weight loss in overweight or obese adults without altering baseline elevated plasma triglyceride concentrations. J Nutr. 2020:
- Passiatore M, Perna A, De-Vitis R, Taccardo G. The use of alfa-lipoic acid-R (ALA-R) in patients with mild-moderate carpal tunnel syndrome: A randomised controlled open label prospective study. Malays Orthop J. 2020;14(1):1-6. PubMed
- El-Nahas MR, Elkannishy G, Abdelhafez H, Elkhamisy ET, El-Sehrawy AA. Oral alpha lipoic acid treatment for symptomatic diabetic peripheral neuropathy: A randomized double-blinded placebo-controlled study. Endocr Metab Immune Disord Drug Targets. 2020. PubMed
- Kim BJ, Hunter A, Brucker AJ, et al. Orally administered alpha lipoic acid as a treatment for geographic atrophy: A randomized clinical trial. Ophthalmol Retina. 2020;4(9):889-898. PubMed
- Derosa G, D'Angelo A, Preti P, Maffioli P. Safety and efficacy of alpha lipoic acid during 4 years of observation: A retrospective, clinical trial in healthy subjects in primary prevention. Drug Des Devel Ther. 2020;14:5367-5374.
- Sun Y, Guan X, Wang H, et al. Randomized clinical trial of combined therapy with oral a-lipoic acid and NB-UVB for nonsegmental stable vitiligo. Dermatol Ther. 2021;34(1):e14610.
- Gilron I, Robb S, Tu D, et al. Double-blind, randomized, placebo-controlled crossover trial of alpha-lipoic acid for the treatment of fibromyalgia pain: the IMPALA trial. Pain. 2021;162(2):561-568. PubMed
- Gullo D, Evans JL, Sortino G, Goldfine ID, Vigneri R. Insulin autoimmune syndrome (Hirata Disease) in European Caucasians taking a-lipoic acid. Clin Endocrinol (Oxf). 2014;81(2):204-9.
- Yukina M, Nuralieva N, Solovyev M, Troshina E, Vasilyev E. Insulin autoimmune syndrome. Endocrinol Diabetes Metab Case Rep. 2020;2020:19-0159. PubMed
- Moffa S, Improta I, Rocchetti S, Mezza T, Giaccari A. Potential cause-effect relationship between insulin autoimmune syndrome and alpha lipoic acid: Two case reports. Nutrition. 2019;57:1-4. PubMed
- Izzo V, Greco C, Corradini D, et al. Insulin autoimmune syndrome in an Argentine woman taking a-lipoic acid: A case report and review of the literature. SAGE Open Med Case Rep. 2018;6:2050313X18819601.
- EFSA Panel on Nutrition, Novel Foods and Food Allergens (NDA), Turck D, et al. Scientific opinion on the relationship between intake of alpha-lipoic acid (thioctic acid) and the risk of insulin autoimmune syndrome. EFSA J 2021;19(6):e06577. PubMed
- Jibril AT, Jayedi A, Shab-Bidar S. Efficacy and safety of oral alpha-lipoic acid supplementation for type 2 diabetes management: a systematic review and dose-response meta-analysis of randomized trials. Endocr Connect 2022;11(10):e220322. PubMed
- Corazza M, Arlotti E, Schettini N, Pacetti L, Bianchi A, Borghi A. Allergic contact dermatitis due to a-lipoic acid in a topical over-the-counter product: A case report. Contact Dermatitis 2023.
- Velasco-Amador JP, Prados-Carmona Á, Navarro-Triviño FJ. Contact urticaria syndrome caused by alpha-lipoic acid in a master formula for vulvar lichen sclerosus. Contact Dermatitis 2023;89(2):136-137. PubMed
- Sehgal T, Ohri U, Mittal N, Attri P, Dishant F. A Case of Insulin Autoimmune Syndrome in an Indian Male Taking Alpha-Lipoic Acid. Cureus 2023;15(8):e43743. PubMed
Acetyl-l-carnitine 22 references
- Thal LJ, Carta A, Clarke WR, et al. A 1-year multicenter placebo-controlled study of acetyl-L-carnitine in patients with Alzheimer's Disease. Neurology 1996;47:705-11. PubMed
- Sano M, Bell K, Cote L, et al. Double-blind parallel design pilot study of acetyl levocarnitine in patients with Alzheimer's Disease. Arch Neurol 1992;49:1137-41. PubMed
- Spagnoli A, Lucca U, Menasce G, et al. Long-term acetyl-L-carnitine treatment in Alzheimer's Disease. Neurology 1991;41:1726-32. PubMed
- Brooks JO 3rd, Yesavage JA, Carta A, Bravi D. Acetyl L-carnitine slows decline in younger patients with Alzheimer's disease: a reanalysis of a double-blind, placebo-controlled study using the trilinear approach. Int Psychoger 1998;10:193-203. PubMed
- Pettegrew JW, Klunk WE, Panchalingam K, et al. Clinical and neurochemical effects of acetyl-L-carnitine in Alzheimer's disease. Neurobiol Aging 1995;16:1-4. PubMed
- Rai G, Wright G, Scott L, et al. Double-blind, placebo controlled study of acetyl-l-carnitine in patients with Alzheimer's dementia. Curr Med Res Opin 1990;11:638-47. PubMed
- Benvenga S, Ruggeri RM, Russo A, et al. Usefulness of L-carnitine, a naturally occurring peripheral antagonist of thyroid hormone action, in iatrogenic hyperthyroidism: a randomized, double-blind, placebo-controlled clinical trial. J Clin Endocrinol Meta
- Montgomery SA, Thal LJ, Amrein R. Meta-analysis of double blind randomized controlled clinical trials of acetyl-L-carnitine versus placebo in the treatment of mild cognitive impairment and mild Alzheimer's disease. Int Clin Psychopharmacol 2003;18:61-71.. PubMed
- Martinez E, Domingo P, Roca-Cusachs A. Potentiation of acenocoumarol action by L-carnitine. J Intern Med 1993;233:94.
- Hudson S, Tabet N. Acetyl-L-carnitine for dementia. Cochrane Database Syst Rev 2003;2:CD003158.. PubMed
- Bachmann HU, Hoffmann A. Interaction of food supplement L-carnitine with oral anticoagulant acenocoumarol. Swiss Med Wkly 2004;134:385. PubMed
- De Grandis D, Minardi C. Acetyl-L-carnitine (levacecarnine) in the treatment of diabetic neuropathy. A long-term, randomised, double-blind, placebo-controlled study. Drugs R D 2002;3:223-31. PubMed
- 12761 Benvenga S, Amato A, Calvani M, Trimarchi F. Effects of carnitine on thyroid hormone action. Ann N Y Acad Sci 2004;1033:158-67. PubMed
- Sima AAF, Calvani M, Mehra M, et al. Acetyl-L-carnitine improves pain, nerve regeneration, and vibratory perception in patients with chronic diabetic neuropathy: An analysis of two randomized, placebo-controlled trials. Diabetes Care 2005;28:89-94.
- Youle, M. and Osio, M. A double-blind, parallel-group, placebo-controlled, multicentre study of acetyl L-carnitine in the symptomatic treatment of antiretroviral toxic neuropathy in patients with HIV-1 infection. HIV.Med. 2007;8(4):241-250.
- Brennan BP, Jensen JE, Hudson JI, Coit CE, Beaulieu A, Pope HG Jr, Renshaw PF, Cohen BM. A placebo-controlled trial of acetyl-L-carnitine and a-lipoic acid in the treatment of bipolar depression. J Clin Psychopharmacol. 2013 Oct;33(5):627-35.
- Ledinek AH, Sajko MC, Rot U. Evaluating the effects of amantadin, modafinil and acetyl-L-carnitine on fatigue in multiple sclerosis--result of a pilot randomized, blind study. Clin Neurol Neurosurg. 2013 Dec;115 Suppl 1:S86-9. PubMed
- Martinotti G, Andreoli S, Reina D, Di Nicola M, Ortolani I, Tedeschi D, Fanella F, Pozzi G, Iannoni E, D'Iddio S, Prof LJ. Acetyl-l-Carnitine in the treatment of anhedonia, melancholic and negative symptoms in alcohol dependent subjects. Prog Neuropsychop PubMed
- Baek SM, Zheng R, Seo EJ, Hwang DY, Kim BH. Pharmacokinetic comparisons of two acetyl-L-carnitine formulations in healthy Korean volunteers. Int J Clin Pharmacol Ther. 2015;53(11):980-6. PubMed
- Goodison G, Overeem K, de Monte V, Siskind D. Mania associated with self-prescribed acetyl-l-carnitine in a man with bipolar I disorder. Australas Psychiatry. 2017;25(1):13-4.
- Bruno A, Pandolfo G, Crucitti M, Lorusso S, Zoccali RA, Muscatello MR. Acetyl-L-Carnitine Augmentation of Clozapine in Partial-Responder Schizophrenia: A 12-Week, Open-Label Uncontrolled Preliminary Study. Clin Neuropharmacol. 2016;39(6):277-80. PubMed
- Veronese N, Stubbs B, Solmi M, Ajnakina O, Carvalho AF, Maggi S. Acetyl-L-Carnitine Supplementation and the Treatment of Depressive Symptoms: A Systematic Review and Meta-Analysis. Psychosom Med. 2018;80(2):154-9. PubMed
Deanol 15 references
- Davies C, Maidment S, Hanley P, et al. Dimethylaminoethanol (DMAE). HSE. Risk assessment document; EH72/2;1997. (TOXLINE).
- Re O. 2-Dimethylaminoethanol (deanol): a brief review of its clinical efficacy and postulated mechanism of action. Curr Ther Res Clin Exp 1974;16:1238-42.
- Pieralisi G, Ripari P, Vecchiet L. Effects of a standardized ginseng extract combined with dimethylaminoethanol bitartrate, vitamins, minerals, and trace elements on physical performance during exercise. Clin Ther 1991;13:373-82.
- George J, Pridmore S, Aldous D. Double blind controlled trial of deanol in tardive dyskinesia. Aust N Z J Psychiatry 1981;15:68-71. PubMed
- Penovich P, Morgan JP, Kerzner B, et al. Double-blind evaluation of deanol in tardive dyskinesia. JAMA 1978;239:1997-8. DOI
- de Montigny C, Chouinard G, Annable L. Ineffectiveness of deanol in tardive dyskinesia: a placebo controlled study. Psychopharmacology (Berl) 1979;65:219-23. PubMed
- Lindeboom SF, Lakke JP. Deanol and physostigmine in the treatment of L-dopa-induced dyskinesias. Acta Neurol Scand 1978;58:134-8. PubMed
- Jus A, Villeneuve A, Gautier J, et al. Deanol, lithium and placebo in the treatment of tardive dyskinesia. A double-blind crossover study. Neuropsychobiology 1978;4:140-9. PubMed
- Lewis JA, Young R. Deanol and methylphenidate in minimal brain dysfunction. Clin Pharmacol Ther 1975;17:534-40. PubMed
- Fisman M, Mersky H, Helmes E. Double-blind trial of 2-dimethylaminoethanol in Alzheimer's disease. Am J Psychiatry 1981;138:970-2. PubMed
- Ferris SH, Sathananthan G, Gershon S, et al. Senile dementia: treatment with deanol. J Am Geriatr Soc 1977;25:241-4. PubMed
- Haug BA, Holzgraefe M. Orofacial and respiratory tardive dyskinesia: potential side effects of 2-dimethylaminoethanol (deanol)? Eur Neurol 1991;31:423-5. PubMed
- Casey DE. Mood alterations during deanol therapy. Psychopharmacology (Berl) 1979;62:187-91. PubMed
- Sergio W. Use of DMAE (2-dimethylaminoethanol) in the induction of lucid dreams. Med Hypotheses 1988;26:255-7. PubMed
- Osol A, Hoover JE, eds. Remington's Pharmaceutical Science, 15th ed. Easton, PA: Mack Publishing Company, 1975.
Nattokinase 9 references
- Suzuki Y, Kondo K, Matsumoto Y, et al. Dietary supplementation of fermented soybean, natto, suppresses intimal thickening and modulates the lysis of mural thrombi after endothelial injury in rat femoral artery. Life Sci 2003;73:1289-98.. PubMed
- Sumi H, Hamada H, Nakanishi K, Hiratani H. Enchancement of fibrinolytic activity in plasma by oral administration of nattokinase. Acta Haematol 1990;84:139-43.
- Chang, Y. Y., Liu, J. S., Lai, S. L., Wu, H. S., and Lan, M. Y. Cerebellar hemorrhage provoked by combined use of nattokinase and aspirin in a patient with cerebral microbleeds. Intern Med 2008;47(5):467-469. PubMed
- Kim, J. Y., Gum, S. N., Paik, J. K., Lim, H. H., Kim, K. C., Ogasawara, K., Inoue, K., Park, S., Jang, Y., and Lee, J. H. Effects of nattokinase on blood pressure: a randomized, controlled trial. Hypertens.Res 2008;31(8):1583-1588. PubMed
- <p>Maruyama M, Sumi H (eds): Effect of natto diet on blood pressure, in Basic and Clinical Aspects of Japanese Traditional Food Natto II. Japan Technology Transfer Association (JTTAS), 1998, pp 1–3.</p>
- Kurosawa Y, Nirengi S, Homma T, et al. A single-dose of oral nattokinase potentiates thrombolysis and anti-coagulation profiles. Sci Rep 2015;5:11601. PubMed
- Ramachandran L, Aqeel A, Jafri A, Sidhu Y, Mohamed Djirdeh T. Nattokinase-associated hemoperitoneum in an elderly woman. Cureus 2021;13(12):e20074. PubMed
- Awatani-Yoshidome K, Hashimoto T, Satoh T. Anaphylaxis from nattokinase in a patient with fermented soybean (natto) allergy. Allergol Int 2022;71(1):153-4. PubMed
- Suzuki K, Nakamura M, Sato N, Futamura K, Matsunaga K, Yagami A. Nattokinase, a subtilisin family serine protease, is a novel allergen contained in the traditional Japanese fermented food natto. Allergol Int 2022.
Phosphatidylserine 9 references
- Crook T, Petrie W, Wells C, Massari DC. Effects of phosphatidylserine in Alzheimer's disease. Psychopharmacol Bull 1992;28:61-6.
- Pepping J. Phosphatidylserine. Am J Health-Syst Pharm 1999;56:2038,2043-4.
- Kidd PM. Phosphatidylserine; Membrane nutrient for memory. A clinical and mechanistic assessment. Altern Med Rev 1996;1:70-84.
- Kim HY, Akbar M, Lau A, et al. Inhibition of neuronal apoptosis by docosahexaenoic acid (22:6n-3). Role of phosphatidylserine in antiapoptotic effect. J Biol Chem 2000;275:35215-23.. PubMed
- Zanotti A, Valzelli L, Toffano G. Chronic phosphatidylserine treatment improves spatial memory and passive avoidance in aged rats. Psychopharmacology (Berl) 1989;99:316-21.. PubMed
- Schreiber S, Kampf-Sherf O, Gorfine M, et al. An open trial of plant-source derived phosphatydilserine for treatment of age-related cognitive decline. Isr J Psychiatry Relat Sci 2000;37:302-7.
- Pepping, J. Phosphatidylserine. Am J Health Syst.Pharm. 10-15-1999;56(20):2038, 2043-2038, 2044.
- Monteverde, A., Gnemmi, P., Rossi, F., Monteverde, A., and Finali, G. C. Selegiline in the treatment of mild to moderate Alzheimer-type dementia. Clin.Ther 1990;12(4):315-322.
- Vakhapova V, Cohen T, Richter Y, Herzog Y, Kam Y, Korczyn AD. Phosphatidylserine containing omega-3 Fatty acids may improve memory abilities in nondemented elderly individuals with memory complaints: results from an open-label extension study. Dement Geri PubMed
Ginkgo 97 references
- Davydov L, Stirling AL. Stevens-Johnson syndrome with Ginkgo biloba. J Herb Pharmacother 2001;1:65-9. DOI
- Benjamin J, Muir T, Briggs K, Pentland B. A case of cerebral haemorrhage-can Ginkgo biloba be implicated? Postgrad Med J 2001;77:112-3.
- Matthews, MK. Association of Ginkgo biloba with intracerebral hemorrhage. Neurology 1998;50:1934.
- Rowin J, Lewis SL. Spontaneous bilateral subdural hemotomas with chronic Ginkgo biloba ingestion. Neurology 1996;46:1775-6.
- Rosenblatt M, Mindel T. Spontaneous hyphema associated with ingestion of Ginkgo biloba extract. N Engl J Med 1997;336:1108.
- Fessenden JM, Wittenborn W, Clarke L. Gingko biloba: a case report of herbal medicine and bleeding postoperatively from a laparoscopic cholecystectomy. Am Surg 2001;67:33-5. DOI
- Gurley BJ, Gardner SF, Hubbard MA. Clinical assessment of potential cytochrome P450-mediated herb-drug interactions. AAPS Ann Mtg & Expo Indianapolis, IN: 2000; Oct 29 - Nov 2:presentation #3460.
- Cohen AJ, Bartlik B. Ginkgo biloba for antidepressant-induced sexual dysfunction. J Sex Marital Ther 1998;24:139-43. PubMed
- Kudolo GB. The effect of 3-month ingestion of Ginkgo biloba extract on pancreatic beta-cell function in response to glucose loading in normal glucose tolerant individuals. J Clin Pharmacol 2000;40:647-54.
- Heck AM, DeWitt BA, Lukes AL. Potential interactions between alternative therapies and warfarin. Am J Health Syst Pharm 2000;57:1221-7. DOI
- Cesarani A, Meloni F, Alpini D, et al. Ginkgo biloba (EGb 761) in the treatment of equilibrium disorders. Adv Ther 1998;15:291-304.
- Galluzzi S, Zanetti O, Binetti G, et al. Coma in a patient with Alzheimer's disease taking low dose trazodone and Ginkgo biloba. J Neurol Neurosurg Psychiatry 2000;68:679-80. DOI
- Budzinski JW, Foster BC, Vandenhoek S, Arnason JT. An in vitro evaluation of human cytochrome P450 3A4 inhibition by selected commercial herbal extracts and tinctures. Phytomedicine 2000;7:273-82. PubMed
- Gregory PJ. Seizure associated with Ginkgo biloba? Ann Intern Med 2001;134:344.
- Granger AS. Ginkgo biloba precipitating epileptic seizures. Age Ageing 2001;30:523-5. PubMed
- Kajiyama Y, Fujii K, Takeuchi H, Manabe Y. Ginkgo seed poisoning. Pediatrics 2002;109:325-7. PubMed
- Miwa H, Iijima M, Tanaka S, Mizuno Y. Generalized convulsions after consuming a large amount of gingko nuts. Epilepsia 2001;42:280-1. DOI
- Burschka MA, Hassan HA, Reineke T, et al. Effect of treatment with Ginkgo biloba extract EGb 761 (oral) on unilateral idiopathic sudden hearing loss in a prospective randomized double-blind study of 106 outpatients. Eur Arch Otorhinolaryngol 2001;258:213- PubMed
- Miller LG, Freeman B. Possible subdural hematoma associated with Ginkgo biloba. J Herb Pharmacother 2002;2:57-63.
- Kudolo GB, Dorsey S, Blodgett J. Effect of the ingestion of Ginkgo biloba extract on platelet aggregation and urinary prostanoid excretion in healthy and Type 2 diabetic subjects. Thromb Res 2002;108:151-60.. PubMed
- Fong KC, Kinnear PE. Retrobulbar haemorrhage associated with chronic Ginkgo biloba ingestion. Postgrad Med J 2003;79:531-2..
- Gurley BJ, Gardner SF, Hubbard MA, et al. Cytochrome P450 phenotypic ratios for predicting herb-drug interactions in humans. Clin Pharmacol Ther 2002;72:276-87.. PubMed
- Kang BJ, Lee SJ, Kim MD, Cho MJ. A placebo-controlled, double-blind trial of Ginkgo biloba for antidepressant-induced sexual dysfunction. Hum Psychopharmacol 2002;17:279-84.
- Yale SH, Glurich I. Analysis of the inhibitory potential of Ginkgo biloba, Echinacea purpurea, and Serenoa repens on the metabolic activity of cytochrome P450 3A4, 2D6, and 2C9. J Altern Complement Med 2005;11:433-9.
- Yasui-Furukori N, Furukori H, Kaneda A, et al. The effects of Ginkgo biloba extracts on the pharmacokinetics and pharmacodynamics of donepezil. J Clin Pharmacol 2004;44:538-42.
- Markowitz JS, Donovan JL, Lindsay DeVane C, et al. Multiple-dose administration of Ginkgo biloba did not affect cytochrome P-450 2D6 or 3A4 activity in normal volunteers. J Clin Psychopharmacol 2003;23:576-81. PubMed
- Arenz A, Kelin M, Flehe K, et al. Occurrence of neurotoxic 4'-O-methylpyridoxine in ginkgo biloba leaves, ginkgo medications and Japanese ginkgo food. Planta Med 1996;62:548-51.
- Engelsen J, Nielsen JD, Winther K. Effect of coenzyme Q10 and Ginkgo biloba on warfarin dosage in stable, long-term warfarin treated outpatients. A randomised, double blind, placebo-crossover trial. Thromb Haemost 2002;87:1075-6. DOI
- Gaudineau C, Beckerman R, Welbourn S, Auclair K. Inhibition of human P450 enzymes by multiple constituents of the Ginkgo biloba extract. Biochem Biophys Res Comm 2004;318:1072–8. PubMed
- Kohler S, Funk P, Kieser M. Influence of a 7-day treatment with Ginkgo biloba special extract EGb 761 on bleeding time and coagulation: a randomized, placebo-controlled, double-blind study in healthy volunteers. Blood Coagul Fibrinolysis 2004;15:303–9. PubMed
- Jiang X, Williams KM, Liauw WS, et al. Effect of ginkgo and ginger on the pharmacokinetics and pharmacodynamics of warfarin in healthy subjects. Br J Clin Pharmacol 2005;59:425-32. PubMed
- Destro MW, Speranzini MB, Cavalheiro Filho C, et al. Bilateral haematoma after rhytidoplasty and blepharoplasty following chronic use of Ginkgo biloba. Br J Plast Surg 2005;58:100-1. PubMed
- Yin OQ, Tomlinson B, Waye MM, et al. Pharmacogenetics and herb-drug interactions: experience with Ginkgo biloba and omeprazole. Pharmacogenetics 2004;14:841-50. PubMed
- Bent S, Goldberg H, Padula A, Avins AL. Spontaneous bleeding associated with Ginkgo biloba: a case report and systematic review of the literature. J Gen Intern Med 2005;20;657-61. DOI
- Meisel C, Johne A, Roots I. Fatal intracerebral mass bleeding associated with Ginkgo biloba and ibuprofen. Atherosclerosis 2003;167:367. PubMed
- Bebbington A, Kulkarni R, Roberts P. Ginkgo biloba: Persistent bleeding after total hip arthroplasty caused by herbal self-medication. J Arthroplasty 2005;20:125-6. .
- Kupiec T, Raj V. Fatal seizures due to potential herb-drug interactions with Ginkgo biloba. J Anal Toxicol 2005:755-8. PubMed
- Hauser D, Gayowski T, Singh N. Bleeding complications precipitated by unrecognized Gingko biloba use after liver transplantation. Transpl Int 2002;15:377-9. DOI
- Mohutsky MA, Anderson GD, Miller JW, Elmer GW. Ginkgo biloba: evaluation of CYP2C9 drug interactions in vitro and in vivo. Am J Ther 2006;13:24-31. PubMed
- Kudolo GB. The effect of 3-month ingestion of Ginkgo biloba extract (EGb 761) on pancreatic beta-cell function in response to glucose loading in individuals with non-insulin-dependent diabetes mellitus. J Clin Pharmacol 2001;41:600-11.
- Pennisi RS. Acute generalised exanthematous pustulosis induced by the herbal remedy Ginkgo biloba. Med J Aust 2006;184:583-4. PubMed
- Yagmur E, Piatkowski A, Groger A, et al. Bleeding complication under Gingko biloba medication. Am J Hematol 2005;79:343-4. PubMed
- Vale S. Subarachnoid haemorrhage associated with Ginkgo biloba. Lancet 1998;352:36. PubMed
- Aruna D, Naidu MU. Pharmacodynamic interaction studies of Ginkgo biloba with cilostazol and clopidogrel in healthy human subjects. Br J Clin Pharmacol 2007;63:333-8.
- Dugoua JJ, Mills E, Perri D, Koren G. Safety and efficacy of ginkgo (Ginkgo biloba) during pregnancy and lactation. Can J Clin Pharmacol 2006;13:e277-84.
- Jiang X, Blair EY, McLachlan AJ. Investigation of the effects of herbal medicines on warfarin response in healthy subjects: a population pharmacokinetic-pharmacodynamic modeling approach. J Clin Pharmacol 2006;46:1370-8. PubMed
- Woelk H, Arnoldt KH, Kieser M, Hoerr R. Ginkgo biloba special extract EGb 761 in generalized anxiety disorder and adjustment disorder with anxious mood: a randomized, double-blind, placebo-controlled trial. J Psychiatr Res 2007;41:472-80. PubMed
- DeKosky ST, Williamson JD, Fitzpatrick AL, et al. Ginkgo biloba for prevention of dementia. JAMA 2008;300:2253-62.
- Dodge HH, Zitzelberger T, Oken BS, et al. A randomized placebo-controlled trial of ginkgo biloba for the prevention of cognitive decline. Neurology 2008;70(19 Pt 2):1809-17. PubMed
- Wiegman DJ, Brinkman K, Franssen EJ. Interaction of Ginkgo biloba with efavirenz. AIDS 2009;23:1184-5. PubMed
- Kim BH, Kim KP, Lim KS, et al. Influence of Ginkgo biloba extract on the pharmacodynamic effects and pharmacokinetic properties of ticlopidine: An open-label, randomized, two-period, two-treatment, two-sequence, single-dose crossover study in healthy Kor
- Salehi B, Imani R, Mohammadi MR, et al. Ginkgo biloba for attention-deficit/hyperactivity disorder in children and adolescents: a double blind, randomized controlled trial. Prog Neuropsychopharmacol Biol Psychiatry 2010;34:76-80. PubMed
- Kellermann AJ, Kloft C. Is there a risk of bleeding associated with standardized ginkgo biloba extract therapy? A systematic review and meta-analysis. Pharmacotherapy 2011;31:490-502.
- Kuller LH, Ives DG, Fitzpatrick AL, et al. Does Ginkgo biloba reduce the risk of cardiovascular events? Circ Cardiovasc Qual Outcomes 2010;3:41-7.
- Naccarato M, Yoong D, Gough K. A potential drug-herbal interaction between Ginkgo biloba and efavirenz. J Int Assoc Physicians AIDS Care (Chic). 2012;11(2):98-100. doi: 10.1177/1545109711435364. Epub 2012 Feb 9.
- Engelsen, J., Nielsen, J. D., and Hansen, K. F. [Effect of Coenzyme Q10 and Ginkgo biloba on warfarin dosage in patients on long-term warfarin treatment. A randomized, double-blind, placebo-controlled cross-over trial]. Ugeskr.Laeger 4-28-2003;165(18):18
- Parsad, D., Pandhi, R., and Juneja, A. Effectiveness of oral Ginkgo biloba in treating limited, slowly spreading vitiligo. Clin Exp.Dermatol. 2003;28(3):285-287.
- Bal Dit, Sollier C., Caplain, H., and Drouet, L. No alteration in platelet function or coagulation induced by EGb761 in a controlled study. Clin Lab Haematol. 2003;25(4):251-253. PubMed
- Yoshioka, M., Ohnishi, N., Koishi, T., Obata, Y., Nakagawa, M., Matsumoto, T., Tagagi, K., Takara, K., Ohkuni, T., Yokoyama, T., and Kuroda, K. Studies on interactions between functional foods or dietary supplements and medicines. IV. Effects of ginkgo b
- Yoshioka, M., Ohnishi, N., Sone, N., Egami, S., Takara, K., Yokoyama, T., and Kuroda, K. Studies on interactions between functional foods or dietary supplements and medicines. III. Effects of ginkgo biloba leaf extract on the pharmacokinetics of nifedipi
- Lovera, J., Bagert, B., Smoot, K., Morris, C. D., Frank, R., Bogardus, K., Wild, K., Oken, B., Whitham, R., and Bourdette, D. Ginkgo biloba for the improvement of cognitive performance in multiple sclerosis: a randomized, placebo-controlled trial. Mult.S PubMed
- Lin, Y. Y., Chu, S. J., and Tsai, S. H. Association between priapism and concurrent use of risperidone and Ginkgo biloba. Mayo Clin Proc 2007;82(10):1289-1290.
- Robertson, S. M., Davey, R. T., Voell, J., Formentini, E., Alfaro, R. M., and Penzak, S. R. Effect of Ginkgo biloba extract on lopinavir, midazolam and fexofenadine pharmacokinetics in healthy subjects. Curr Med Res Opin 2008;24(2):591-599. PubMed
- Penzak, S. R., Busse, K. H., Robertson, S. M., Formentini, E., Alfaro, R. M., and Davey, R. T., Jr. Limitations of using a single postdose midazolam concentration to predict CYP3A-mediated drug interactions. J Clin Pharmacol 2008;48(6):671-680. PubMed
- May, B. H., Yang, A. W., Zhang, A. L., Owens, M. D., Bennett, L., Head, R., Cobiac, L., Li, C. G., Hugel, H., Story, D. F., and Xue, C. C. Chinese herbal medicine for Mild Cognitive Impairment and Age Associated Memory Impairment: a review of randomised
- Choi, W. S., Choi, C. J., Kim, K. S., Lee, J. H., Song, C. H., Chung, J. H., Ock, S. M., Lee, J. B., and Kim, C. M. To compare the efficacy and safety of nifedipine sustained release with Ginkgo biloba extract to treat patients with primary Raynaud's phe
- Lei, H. P., Wang, G., Wang, L. S., Ou-yang, D. S., Chen, H., Li, Q., Zhang, W., Tan, Z. R., Fan, L., He, Y. J., and Zhou, H. H. Lack of effect of Ginkgo biloba on voriconazole pharmacokinetics in Chinese volunteers identified as CYP2C19 poor and extensiv
- Russo, V., Stella, A., Appezzati, L., Barone, A., Stagni, E., Roszkowska, A., and Delle, Noci N. Clinical efficacy of a Ginkgo biloba extract in the topical treatment of allergic conjunctivitis. Eur J Ophthalmol. 2009;19(3):331-336. PubMed
- Fan, L., Tao, G. Y., Wang, G., Chen, Y., Zhang, W., He, Y. J., Li, Q., Lei, H. P., Jiang, F., Hu, D. L., Huang, Y. F., and Zhou, H. H. Effects of Ginkgo biloba extract ingestion on the pharmacokinetics of talinolol in healthy Chinese volunteers. Ann Phar PubMed
- Ozgoli, G., Selselei, E. A., Mojab, F., and Majd, H. A. A randomized, placebo-controlled trial of Ginkgo biloba L. in treatment of premenstrual syndrome. J Altern.Complement Med 2009;15(8):845-851.
- Singh, V., Singh, S. P., and Chan, K. Review and meta-analysis of usage of ginkgo as an adjunct therapy in chronic schizophrenia. Int J Neuropsychopharmacol. 2010;13(2):257-271.
- Kim, T. E., Kim, B. H., Kim, J., Kim, K. P., Yi, S., Shin, H. S., Lee, Y. O., Lee, K. H., Shin, S. G., Jang, I. J., and Yu, K. S. Comparison of the pharmacokinetics of ticlopidine between administration of a combined fixed-dose tablet formulation of ticl
- Nicolai, S. P., Gerardu, V. C., Kruidenier, L. M., Prins, M. H., and Teijink, J. A. From the Cochrane library: Ginkgo biloba for intermittent claudication. Vasa 2010;39(2):153-158. PubMed
- Patel, N. Herbal remedies. Br.Dent.J 8-28-2010;209(4):153.
- Pedroso, J. L., Henriques Aquino, C. C., Escorcio Bezerra, M. L., Baiense, R. F., Suarez, M. M., Dutra, L. A., Braga-Neto, P., and Povoas Barsottini, O. G. Ginkgo biloba and cerebral bleeding: a case report and critical review. Neurologist. 2011;17(2):89 PubMed
- Russo, V., Rago, A., Russo, G. M., Calabro, R., and Nigro, G. Ginkgo biloba: an ancient tree with new arrhythmic side effects. J Postgrad.Med 2011;57(3):221.
- Zhou, Y. and Zeng, R. [Effects of Ginkgo biloba extract on anticoagulation and blood drug level of warfarin in healthy wolunteers]. Zhongguo Zhong Yao Za Zhi 2011;36(16):2290-2293. DOI
- Skogh, M. Extracts of Ginkgo biloba and bleeding or haemorrhage. Lancet 10-3-1998;352(9134):1145-1146. PubMed
- Fessenden JM, Wittenborn W, and Clarke L. Ginkgo biloba: a case report of herbal medicine and bleeding postoperatively from a laparoscopic cholecystectomy. Am Surg 2001;67(1):33-35.
- Burkard G. [The efficacy and safety of ginkgo biloba extract in dementia]. Fortschr Med [Supp] 1991;109(107):6-8.
- Dai LL, Fan L, Wu HZ, Tan ZR, Chen Y, Peng XD, Shen MX, Yang GP, Zhou HH. Assessment of a pharmacokinetic and pharmacodynamic interaction between simvastatin and Ginkgo biloba extracts in healthy subjects. Xenobiotica 2013;43(10):862-7.
- Guo CX, Pei Q, Yin JY, Peng XD, Zhou BT, Zhao YC, Wu LX, Meng XG, Wang G, Li Q, Ouyang DS, Liu ZQ, Zhang W, Zhou HH. Effects of Ginkgo biloba extracts on pharmacokinetics and efficacy of atorvastatin based on plasma indices. Xenobiotica 2012;42(8):784-90.
- Stoddard GJ, Archer M, Shane-McWhorter L, Bray BE, Redd DF, Proulx J, Zeng-Treitler Q. Ginkgo and Warfarin Interaction in a Large Veterans Administration Population. AMIA Annu Symp Proc. 2015 Nov 5;2015:1174-83.
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Carlile PV. Unexplained alveolar hemorrhage associated with ginkgo and ginseng use. J Bronchology Interv Pulmonol. 2015;22(2):170-2. doi: 10.1097/LBR.0000000000000150. PubMed
- Han EJ, Park HL, Kim SH. Allergic Reaction to Ginkgo Nut on FDG PET/CT. Clin Nucl Med. 2016 Sep;41(9):716-7. doi: 10.1097/RLU.0000000000001276. PubMed
- Rho SS, Woo YS, Bahk WM. Ginkgo biloba induced mood dysregulation: a case report. BMC Complement Altern Med. 2018 Jan 15;18(1):14. PubMed
- Aziz TA, Hussain SA, Mahwi TO, Ahmed ZA, Rahman HS, Rasedee A. The efficacy and safety of Ginkgo biloba extract as an adjuvant in type 2 diabetes mellitus patients ineffectively managed with metformin: a double-blind, randomized, placebo-controlled trial.
- World Health Organization. WHO pharmaceuticals newsletter: 2020, No. 3. Available at: https://www.who.int/medicines/publications/WHO_Pharmaceuticals_Newslet3_20.pdf?ua=1. Accessed June 23, 2021.
- Health Canada. Ginkgo biloba-containing products and the risk of cardiac arrhythmias. Health Product InfoWatch. February 2021. Available at: https://www.canada.ca/en/health-canada/services/drugs-health-products/medeffect-canada/health-product-infowatch/fe
- Wasef AK, Wahdan SA, Saeed NM, El-Demerdash E. Effects of aged garlic and ginkgo biloba extracts on the pharmacokinetics of sofosbuvir in rats. Biopharm Drug Dispos. 2022;43(4):152-62. PubMed
- Xing X, Kong M, Hou Q, Li J, Qian W, Chen X, Li H, Yang C. Effects of ginkgo leaf tablet on the pharmacokinetics of rosiglitazone in rats and its potential mechanism. Pharm Biol. 2022;60(1):1190-7. PubMed
- Hoerr R, Zimmermann A, Seitz F, Dienel A. Single and repeated doses of EGb 761® do not affect pharmacokinetics or pharmacodynamics of rivaroxaban in healthy subjects. Front Pharmacol. 2022 Apr 20;13:868843. PubMed
- Bai J, Zhang C. Metabolic interaction between biflavonoids in Ginkgo biloba leaves and tacrolimus. Biopharm Drug Dispos 2023;44(2):157-164.
- Wang Q, Liu Z, Wang R, et al. Effect of Ginkgo biloba extract on pharmacology and pharmacokinetics of atorvastatin in rats with hyperlipidaemia. Food Funct 2023;14(7):3051-3066.
- Burnett CL, Bergfeld WF, Belsito DV, et al. Safety Assessment of Ginkgo biloba-Derived Ingredients as Used in Cosmetics. Int J Toxicol. 2023 Nov 6:10915818231210792.
- Yao Y, Zhao J, Li C, et al. Ginkgo biloba extract safety: Insights from a real-world pharmacovigilance study of FDA adverse event reporting system (FAERS) events. J Ethnopharmacol 2025;337(Pt 3):119010. PubMed
Huperzine A 13 references
- Skolnick AA. Old Chinese herbal medicine used for fever yields possible new Alzheimer Disease therapy. JAMA 1997;277:776. DOI
- Ye JW, Cai JX, Wang LM, Tang XC. Improving effects of huperzine A on spatial working memory in aged monkeys and young adult monkeys with experimental cognitive impairment. J Pharmacol Exp Ther 1999;288:814-9.. DOI
- Wang T, Tang XC. Reversal of scopolamine-induced deficits in radial maze performance by (-)-huperzine A: comparison with E2020 and tacrine. Eur J Pharmacol 1998;349:137-42. PubMed
- Xu SS, Gao ZX, Weng Z, et al. Efficacy of tablet huperzine-A on memory, cognition, and behavior in Alzheimer's disease. Zhongguo Yao Li Xue Bao 1995;16:391-5.
- Zhang RW, Tang XC, Han YY, et al. [Drug evaluation of huperzine A in the treatment of senile memory disorders]. Chung Kuo Yao Li Hsueh Pao 1991;12:250-2.
- Xu SS, Cai ZY, Qu ZW, et al. Huperzine-A in capsules and tablets for treating patients with Alzheimer disease. Zhongguo Yao Li Xue Bao 1999;20:486-90.
- Felgenhauer N, Zilker T, Worek F, Eyer P. Intoxication with huperzine A, a potent anticholinesterase found in the fir club moss. J Toxicol Clin Toxicol 2000;38:803-8.. PubMed
- Zhang, Z., Wang, X., Chen, Q., Shu, L., Wang, J., and Shan, G. [Clinical efficacy and safety of huperzine Alpha in treatment of mild to moderate Alzheimer disease, a placebo-controlled, double-blind, randomized trial]. Zhonghua Yi Xue Za Zhi 7-25-2002;82
- Cheng, D. H., Ren, H., and Tang, X. C. Huperzine A, a novel promising acetylcholinesterase inhibitor. Neuroreport 12-20-1996;8(1):97-101. PubMed
- Wang BS, Wang H, Wei ZH, Song YY, Zhang L, Chen HZ. Efficacy and safety of natural acetylcholinesterase inhibitor huperzine A in the treatment of Alzheimer's disease: an updated meta-analysis. J Neural Transm (Vienna) 2009;116(4):457-65. PubMed
- Xu ZQ, Liang XM, Juan-Wu, Zhang YF, Zhu CX, Jiang XJ. Treatment with Huperzine A improves cognition in vascular dementia patients. Cell Biochem Biophys 2012;62(1):55-8. PubMed
- Yang G, Wang Y, Tian J, Liu JP. Huperzine A for Alzheimer's disease: a systematic review and meta-analysis of randomized clinical trials. PLoS One 2013;8(9):e74916. PubMed
- Xing SH, Zhu CX, Zhang R, An L. Huperzine a in the treatment of Alzheimer's disease and vascular dementia: a meta-analysis. Evid Based Complement Alternat Med 2014;2014:363985. PubMed
Green Tea 219 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Harder S, Fuhr U, Staib AH, Wolff T. Ciprofloxacin-caffeine: a drug interaction established using in vivo and in vitro investigations. Am J Med 1989;87:89S-91S. PubMed
- Carbo M, Segura J, De la Torre R, et al. Effect of quinolones on caffeine disposition. Clin Pharmacol Ther 1989;45:234-40. PubMed
- Healy DP, Polk RE, Kanawati L, et al. Interaction between oral ciprofloxacin and caffeine in normal volunteers. Antimicrob Agents Chemother 1989;33:474-8. PubMed
- Mester R, Toren P, Mizrachi I, et al. Caffeine withdrawal increases lithium blood levels. Biol Psychiatry 1995;37:348-50. PubMed
- Jefferson JW. Lithium tremor and caffeine intake: two cases of drinking less and shaking more. J Clin Psychiatry 1988;49:72-3.
- Mitscher LA, Mitscher LA, Jung M, Shankel D, et al. Chemoprotection: a review of the potential therapeutic antioxidant properties of green tea (Camellia sinensis) and certain of its constituents. Med Res Rev 1997;17:327-65.
- Joeres R, Klinker H, Heusler H, et al. Influence of mexiletine on caffeine elimination. Pharmacol Ther 1987;33:163-9. PubMed
- Vahedi K, Domingo V, Amarenco P, Bousser MG. Ischemic stroke in a sportsman who consumed MaHuang extract and creatine monohydrate for bodybuilding. J Neurol Neurosurg Psychiatr 2000;68:112-3.
- Wakabayashi K, Kono S, Shinchi K, et al. Habitual coffee consumption and blood pressure: A study of self-defense officials in Japan. Eur J Epidemiol 1998;14:669-73. PubMed
- Hodgson JM, Puddey IB, Burke V, et al. Effects on blood pressure of drinking green and black tea. J Hypertens 1999;17:457-63. PubMed
- Booth SL, Madabushi HT, Davidson KW, et al. Tea and coffee brews are not dietary sources of vitamin K-1 (phylloquinone). J Am Diet Assoc 1995;95:82-3. PubMed
- Lou FQ, Zhang MF, Zhang XG, et al. A study on tea-pigment in prevention of atherosclerosis. Chin Med J (Engl) 1989;102:579-83.
- Graham HN. Green tea composition, consumption, and polyphenol chemistry. Prev Med 1992;21:334-50. PubMed
- Rapuri PB, Gallagher JC, Kinyamu HK, Ryschon KL. Caffeine intake increases the rate of bone loss in elderly women and interacts with vitamin D receptor genotypes. Am J Clin Nutr 2001;74:694-700. PubMed
- The National Toxicology Program (NTP). Caffeine. Center for the Evaluation of Risks to Human Reproduction (CERHR). Available at: http://cerhr.niehs.nih.gov/common/caffeine.html.
- Klebanoff MA, Levine RJ, DerSimonian R, et al. Maternal serum paraxanthine, a caffeine metabolite, and the risk of spontaneous abortion. N Engl J Med 1999;341:1639-44. PubMed
- Eskenazi B. Caffeine—filtering the facts. N Engl J Med 1999;341:1688-9. PubMed
- Fernandes O, Sabharwal M, Smiley T, et al. Moderate to heavy caffeine consumption during pregnancy and relationship to spontaneous abortion and abnormal fetal growth: a meta-analysis. Reprod Toxicol 1998;12:435-44. PubMed
- Pollock BG, Wylie M, Stack JA, et al. Inhibition of caffeine metabolism by estrogen replacement therapy in postmenopausal women. J Clin Pharmacol 1999;39:936-40. PubMed
- Dews PB, Curtis GL, Hanford KJ, O'Brien CP. The frequency of caffeine withdrawal in a population-based survey and in a controlled, blinded pilot experiment. J Clin Pharmacol 1999;39:1221-32. PubMed
- FDA. Proposed rule: dietary supplements containing ephedrine alkaloids. Available at: www.verity.fda.gov (Accessed 25 January 2000).
- Weisburger JH. Tea and health: the underlying mechanisms. Proc Soc Exp Biol Med 1999;220:271-5. PubMed
- Taylor JR, Wilt VM. Probable antagonism of warfarin by green tea. Ann Pharmacother 1999;33:426-8. PubMed
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Hagg S, Spigset O, Mjorndal T, Dahlqvist R. Effect of caffeine on clozapine pharmacokinetics in healthy volunteers. Br J Clin Pharmacol 2000;49:59-63. PubMed
- Watson JM, Jenkins EJ, Hamilton P, et al. Influence of caffeine on the frequency and perception of hypoglycemia in free-living patients with type 1 diabetes. Diabetes Care 2000;23:455-9. PubMed
- Lloyd T, Johnson-Rollings N, Eggli DF, et al. Bone status among postmenopausal women with different habitual caffeine intakes: a longitudinal investigation. J Am Coll Nutr 2000;19:256-61. PubMed
- American Academy of Pediatrics. The transfer of drugs and other chemicals into human milk. Pediatrics 2001;108:776-89. PubMed
- Heck AM, DeWitt BA, Lukes AL. Potential interactions between alternative therapies and warfarin. Am J Health Syst Pharm 2000;57:1221-7. DOI
- Sinclair CJ, Geiger JD. Caffeine use in sports. A pharmacological review. J Sports Med Phys Fitness 2000;40:71-9.
- Haller CA, Benowitz NL. Adverse cardiovascular and central nervous system events associated with dietary supplements containing ephedra alkaloids. N Engl J Med 2000;343:1833-8. PubMed
- Ali M, Afzal M. A potent inhibitor of thrombin stimulated platelet thromboxane formation from unprocessed tea. Prostaglandins Leukot Med 1987;27:9-13. PubMed
- Ardlie NG, Glew G, Schultz BG, Schwartz CJ. Inhibition and reversal of platelet aggregation by methyl xanthines. Thromb Diath Haemorrh 1967;18:670-3. DOI
- Ferrini RL, Barrett-Connor E. Caffeine intake and endogenous sex steroid levels in postmenopausal women. The Rancho Bernardo Study. Am J Epidemiol 1996:144:642-4. PubMed
- Pisters KM, Newman RA, Coldman B, et al. Phase I trial of oral green tea extract in adult patients with solid tumors. J Clin Oncol 2001;19:1830-8. PubMed
- Haller CA, Jacob P 3rd, Benowitz NL. Pharmacology of ephedra alkaloids and caffeine after single-dose dietary supplement use. Clin Pharmacol Ther 2002;71:421-32. PubMed
- Bell DG, Jacobs I, Ellerington K. Effect of caffeine and ephedrine ingestion on anaerobic exercise performance. Med Sci Sports Exerc 2001;33:1399-403. PubMed
- Horner NK, Lampe JW. Potential mechanisms of diet therapy for fibrocystic breast conditions show inadequate evidence of effectiveness. J Am Diet Assoc 2000;100:1368-80. PubMed
- Bracken MB, Triche EW, Belanger K, et al. Association of maternal caffeine consumption with decrements in fetal growth. Am J Epidemiol 2003;157:456-66.. PubMed
- McGowan JD, Altman RE, Kanto WP Jr. Neonatal withdrawal symptoms after chronic maternal ingestion of caffeine. South Med J 1988;81:1092-4.. PubMed
- Nehlig A, Debry G. Consequences on the newborn of chronic maternal consumption of coffee during gestation and lactation: a review. J Am Coll Nutr 1994;13:6-21.. PubMed
- Massey LK. Is caffeine a risk factor for bone loss in the elderly? Am J Clin Nutr 2001;74:569-70. PubMed
- Kockler DR, McCarthy MW, Lawson CL. Seizure activity and unresponsiveness after hydroxycut ingestion. Pharmacotherapy 2001;21:647-51.. PubMed
- Nix D, Zelenitsky S, Symonds W, et al. The effect of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. Clin Pharmacol Ther 1992;51:183. DOI
- Ahn WS, Yoo J, Huh SW, et al. Protective effects of green tea extracts (polyphenon E and EGCG) on human cervical lesions. Eur J Cancer Prev 2003;12:383-90. PubMed
- Infante S, Baeza ML, Calvo M, et al. Anaphylaxis due to caffeine. Allergy 2003;58:681-2. PubMed
- Massey LK, Whiting SJ. Caffeine, urinary calcium, calcium metabolism and bone. J Nutr 1993;123:1611-4. PubMed
- Shirai T, Hayakawa H, Akiyama J, et al. Food allergy to green tea. J Allergy Clin Immunol 2003;112:805-6. PubMed
- Jatoi A, Ellison N, Burch PA, et al. A phase II trial of green tea in the treatment of patients with androgen independent metastatic prostate carcinoma. Cancer 2003;97:1442-6.. PubMed
- Nawrot P, Jordan S, Eastwood J, et al. Effects of caffeine on human health. Food Addit Contam 2003;20:1-30. PubMed
- May DC, Jarboe CH, VanBakel AB, Williams WM. Effects of cimetidine on caffeine disposition in smokers and nonsmokers. Clin Pharmacol Ther 1982;31:656-61. PubMed
- Brown NJ, Ryder D, Branch RA. A pharmacodynamic interaction between caffeine and phenylpropanolamine. Clin Pharmacol Ther 1991;50:363-71. PubMed
- Sanderink GJ, Bournique B, Stevens J, et al. Involvement of human CYP1A isoenzymes in the metabolism and drug interactions of riluzole in vitro. Pharmacol Exp Ther 1997;282:1465-72. DOI
- Wahllander A, Paumgartner G. Effect of ketoconazole and terbinafine on the pharmacokinetics of caffeine in healthy volunteers. Eur J Clin Pharmacol 1989;37:279-83. PubMed
- Carrillo JA, Benitez J. Clinically significant pharmacokinetic interactions between dietary caffeine and medications. Clin Pharmacokinet 2000;39:127-53. PubMed
- Underwood DA. Which medications should be held before a pharmacologic or exercise stress test? Cleve Clin J Med 2002;69:449-50. PubMed
- Aqel RA, Zoghbi GJ, Trimm JR, et al. Effect of caffeine administered intravenously on intracoronary-administered adenosine-induced coronary hemodynamics in patients with coronary artery disease. Am J Cardiol 2004;93:343-6. PubMed
- Zheng XM, Williams RC. Serum caffeine levels after 24-hour abstention: clinical implications on dipyridamole (201)Tl myocardial perfusion imaging. J Nucl Med Technol 2002;30:123-7.
- Institute of Medicine. Caffeine for the Sustainment of Mental Task Performance: Formulations for Military Operations. Washington, DC: National Academy Press, 2001. Available at: http://books.nap.edu/books/0309082587/html/index.html. DOI
- Dews PB, O'Brien CP, Bergman J. Caffeine: behavioral effects of withdrawal and related issues. Food Chem Toxicol 2002;40:1257-61. PubMed
- Beach CA, Mays DC, Guiler RC, et al. Inhibition of elimination of caffeine by disulfiram in normal subjects and recovering alcoholics. Clin Pharmacol Ther 1986;39:265-70. PubMed
- Yang YC, Lu FH, Wu JS, et al. The protective effect of habitual tea consumption on hypertension. Arch Intern Med 2004 26;164:1534-40. PubMed
- Son DJ, Cho MR, Jin YR, et al. Antiplatelet effect of green tea catechins: a possible mechanism through arachidonic acid pathway. Prostaglandins Leukot Essent Fatty Acids 2004;71:25-31. PubMed
- Juliano LM, Griffiths RR. A critical review of caffeine withdrawal: empirical validation of symptoms and signs, incidence, severity, and associated features. Psychopharmacology (Berl) 2004;176:1-29. PubMed
- Winkelmayer WC, Stampfer MJ, Willett WC, Curhan GC. Habitual caffeine intake and the risk of hypertension in women. JAMA 2005;294:2330-5. PubMed
- Raaska K, Raitasuo V, Laitila J, Neuvonen PJ. Effect of caffeine-containing versus decaffeinated coffee on serum clozapine concentrations in hospitalised patients. Basic Clin Pharmacol Toxicol 2004;94:13-8. DOI
- Forrest WH Jr, Bellville JW, Brown BW Jr. The interaction of caffeine with pentobarbital as a nighttime hypnotic. Anesthesiology 1972;36:37-41. PubMed
- Lake CR, Rosenberg DB, Gallant S, et al. Phenylpropanolamine increases plasma caffeine levels. Clin Pharmacol Ther 1990;47:675-85. PubMed
- Bonkovsky HL. Hepatotoxicity associated with supplements containing Chinese green tea (Camellia sinensis). Ann Intern Med 2006;144:68-71.
- Gloro R, Hourmand-Ollivier I, Mosquet B, et al. Fulminant hepatitis during self-medication with hydroalcoholic extract of green tea. Eur J Gastroenterol Hepatol 2005;17:1135-7. PubMed
- Donovan JL, Chavin KD, Devane CL, et al. Green tea (Camellia sinensis) extract does not alter cytochrome P450 3A4 or 2D6 activity in healthy volunteers. Drug Metab Dispos 2004;32:906-8. PubMed
- Chu KO, Wang CC, Chu CY, et al. Pharmacokinetic studies of green tea catechins in maternal plasma and fetuses in rats. J Pharm Sci 2006;95:1372-81. PubMed
- Isbrucker RA, Edwards JA, Wolz E, et al. Safety studies on epigallocatechin gallate (EGCG) preparations. Part 3: teratogenicity and reproductive toxicity studies in rats. Food Chem Toxicol 2006;44:651-61. PubMed
- Navarro-Peran E, Cabezas-Herrera J, Garcia-Canovas F, et al. The antifolate activity of tea catechins. Cancer Res 2005;65:2059-64. PubMed
- Jimenez-Saenz M, Martinez-Sanchez, MDC. Acute hepatitis associated with the use of green tea infusions. J Hepatol 2006;44:616-9. PubMed
- Bradley Pharmaceuticals. Veregen Prescribing Information. October 2006.
- Correa A, Stolley A, Liu Y. Prenatal tea consumption and risks of anencephaly and spina bifida. Ann Epidemiol 2000;10:476-7. PubMed
- Weng X, Odouli R, Li DK. Maternal caffeine consumption during pregnancy and the risk of miscarriage: a prospective cohort study. Am J Obstet Gynecol 2008;198:279.e1-8. PubMed
- Savitz DA, Chan RL, Herring AH, et al. Caffeine and miscarriage risk. Epidemiology 2008;19:55-62. PubMed
- Golden ED, Lam PY, Kardosh A, et al. Green tea polyphenols block the anticancer effects of bortezomib and other boronic acid-based proteasome inhibitors. Blood 2009;113:5927-37. PubMed
- Misaka S, Yatabe J, Muller F, et al. Green Tea Ingestion Greatly Reduces Plasma Concentrations of Nadolol in Healthy Subjects. Clin Pharmacol Ther 2014. [Epub ahead of print]. PubMed
- Roth M, Timmermann BN, Hagenbuch B. Interactions of green tea catechins with organic anion-transporting polypeptides. Drug Metab Dispos 2011;39:920-6. PubMed
- Kato Y, Miyazaki T, Kano T, et al. Involvement of influx and efflux transport systems in gastrointestinal absorption of celiprolol. J Pharm Sci 2009;98:2529-39. PubMed
- Chan, H. T., So, L. T., Li, S. W., Siu, C. W., Lau, C. P., and Tse, H. F. Effect of herbal consumption on time in therapeutic range of warfarin therapy in patients with atrial fibrillation. J.Cardiovasc.Pharmacol. 2011;58(1):87-90. PubMed
- Nishikawa, M., Ariyoshi, N., Kotani, A., Ishii, I., Nakamura, H., Nakasa, H., Ida, M., Nakamura, H., Kimura, N., Kimura, M., Hasegawa, A., Kusu, F., Ohmori, S., Nakazawa, K., and Kitada, M. Effects of continuous ingestion of green tea or grape seed extrac
- Shet, M. S., McPhaul, M., Fisher, C. W., Stallings, N. R., and Estabrook, R. W. Metabolism of the antiandrogenic drug (Flutamide) by human CYP1A2. Drug Metab Dispos. 1997;25(11):1298-1303.
- Staib, A. H., Stille, W., Dietlein, G., Shah, P. M., Harder, S., Mieke, S., and Beer, C. Interaction between quinolones and caffeine. Drugs 1987;34 Suppl 1:170-174. PubMed
- Stille, W., Harder, S., Mieke, S., Beer, C., Shah, P. M., Frech, K., and Staib, A. H. Decrease of caffeine elimination in man during co-administration of 4-quinolones. J.Antimicrob.Chemother. 1987;20(5):729-734. PubMed
- Fuhr, U., Strobl, G., Manaut, F., Anders, E. M., Sorgel, F., Lopez-de-Brinas, E., Chu, D. T., Pernet, A. G., Mahr, G., Sanz, F., and . Quinolone antibacterial agents: relationship between structure and in vitro inhibition of the human cytochrome P450 isof
- Kot, M. and Daniel, W. A. Effect of diethyldithiocarbamate (DDC) and ticlopidine on CYP1A2 activity and caffeine metabolism: an in vitro comparative study with human cDNA-expressed CYP1A2 and liver microsomes. Pharmacol Rep. 2009;61(6):1216-1220. PubMed
- Gasior, M., Borowicz, K., Buszewicz, G., Kleinrok, Z., and Czuczwar, S. J. Anticonvulsant activity of phenobarbital and valproate against maximal electroshock in mice during chronic treatment with caffeine and caffeine discontinuation. Epilepsia 1996;37(3 PubMed
- Jankiewicz, K., Chroscinska-Krawczyk, M., Blaszczyk, B., and Czuczwar, S. J. [Caffeine and antiepileptic drugs: experimental and clinical data]. Przegl.Lek. 2007;64(11):965-967.
- Luszczki, J. J., Zuchora, M., Sawicka, K. M., Kozinska, J., and Czuczwar, S. J. Acute exposure to caffeine decreases the anticonvulsant action of ethosuximide, but not that of clonazepam, phenobarbital and valproate against pentetrazole-induced seizures i
- Chroscinska-Krawczyk, M., Jargiello-Baszak, M., Walek, M., Tylus, B., and Czuczwar, S. J. Caffeine and the anticonvulsant potency of antiepileptic drugs: experimental and clinical data. Pharmacol.Rep. 2011;63(1):12-18. PubMed
- Vaz, J., Kulkarni, C., David, J., and Joseph, T. Influence of caffeine on pharmacokinetic profile of sodium valproate and carbamazepine in normal human volunteers. Indian J.Exp.Biol. 1998;36(1):112-114.
- Gasior, M., Swiader, M., Przybylko, M., Borowicz, K., Turski, W. A., Kleinrok, Z., and Czuczwar, S. J. Felbamate demonstrates low propensity for interaction with methylxanthines and Ca2+ channel modulators against experimental seizures in mice. Eur.J Phar PubMed
- Mohiuddin, M., Azam, A. T., Amran, M. S., and Hossain, M. A. In vive effects of gliclazide and metformin on the plasma concentration of caffeine in healthy rats. Pak.J Biol Sci 5-1-2009;12(9):734-737.
- Mays, D. C., Camisa, C., Cheney, P., Pacula, C. M., Nawoot, S., and Gerber, N. Methoxsalen is a potent inhibitor of the metabolism of caffeine in humans. Clin.Pharmacol.Ther. 1987;42(6):621-626. PubMed
- Wojcikowski, J. and Daniel, W. A. Perazine at therapeutic drug concentrations inhibits human cytochrome P450 isoenzyme 1A2 (CYP1A2) and caffeine metabolism--an in vitro study. Pharmacol Rep. 2009;61(5):851-858. PubMed
- Daniel, W. A., Syrek, M., Rylko, Z., and Kot, M. Effects of phenothiazine neuroleptics on the rate of caffeine demethylation and hydroxylation in the rat liver. Pol.J Pharmacol 2001;53(6):615-621.
- Norager, C. B., Jensen, M. B., Weimann, A., and Madsen, M. R. Metabolic effects of caffeine ingestion and physical work in 75-year old citizens. A randomized, double-blind, placebo-controlled, cross-over study. Clin Endocrinol (Oxf) 2006;65(2):223-228. PubMed
- Wang, X. and Yeung, J. H. Effects of the aqueous extract from Salvia miltiorrhiza Bunge on caffeine pharmacokinetics and liver microsomal CYP1A2 activity in humans and rats. J Pharm Pharmacol 2010;62(8):1077-1083.
- Kot M, Daniel WA. Caffeine as a marker substrate for testing cytochrome P450 activity in human and rat. Pharmacol Rep 2008;60:789-97.
- Kjaerstad MB, Nielsen F, Nohr-Jensen L, et al. Systemic uptake of miconazole during vaginal suppository use and effect on CYP1A2 and CYP3A4 associated enzyme activities in women. Eur J Clin Pharmacol 2010;66:1189-97. PubMed
- Goh BC, Reddy NJ, Dandamudi UB, et al. An evaluation of the drug interaction potential of pazopanib, an oral vascular endothelial growth factor receptor tyrosine kinase inhibitor, using a modified Cooperstown 5+1 cocktail in patients with advanced solid t
- Chen Y, Kang Z, Yan J, et al. Liu wei di huang wan, a well-known traditional Chinese medicine induces CYP1A2 while suppressing CYP2A6 and N-acetyltransferase 2 acivities in man. J Ethnopharmacol 2010;132:213-8.
- Suzuki S, Murayama Y, Sugiyama E, et al. Estimating pediatric doses of drugs metabolized by cytochrome P450 (CYP) isozymes, based on physiological liver development and serum protein levels. Yakugaku Zasshi 2010;130:613-20. PubMed
- Chien CF, Wu YT, Lee WC, et al. Herb-drug interaction of Andrographis paniculata extract and andrographolide on the pharmacokinetics of theophylline in rats. Chem Biol Interact 2010;184:458-65. PubMed
- Mills BM, Zaya MJ, Walters RR, et al. Current cytochrome P450 phenotyping methods applied to metabolic drug -drug interaction prediction in dogs. Drug Metab Dispos 2010;38:396-404. PubMed
- Turpault S, Brian W, Van Horn R, et al. Pharmacokinetic assessment of a five-probe cocktail for CYPs 1A2, 2C9, 2C19, 2D6, and 3A. Br J Clin Pharmacol 2009;68:928-35. PubMed
- Filimonova AA, Ziganshina LE, Ziganshin AU, Chichirov AA. On the possibility of patient phenotyping on the basis of cytochrome p-450 1A2 isoenzyme activity using caffeine as the test substrate. Eksp Klin Farmakol 2009;72:61-5.
- Jenkins J, Williams D, Deng Y, et al. Eltrombopag, an oral thrombopoietin receptor agonist, has no impact on the pharmacokinetic profile of probe drugs for cytochrome P450 isoenzymes CYP3A4, CYP1A2, CYP2C9 and CYP2C19 in healthy men: a cocktail analysis.
- Chow, H. H., Cai, Y., Hakim, I. A., Crowell, J. A., Shahi, F., Brooks, C. A., Dorr, R. T., Hara, Y., and Alberts, D. S. Pharmacokinetics and safety of green tea polyphenols after multiple-dose administration of epigallocatechin gallate and polyphenon E i
- Gross, G., Meyer, K. G., Pres, H., Thielert, C., Tawfik, H., and Mescheder, A. A randomized, double-blind, four-arm parallel-group, placebo-controlled Phase II/III study to investigate the clinical efficacy of two galenic formulations of Polyphenon E in
- Stockfleth, E., Beti, H., Orasan, R., Grigorian, F., Mescheder, A., Tawfik, H., and Thielert, C. Topical Polyphenon E in the treatment of external genital and perianal warts: a randomized controlled trial. Br.J Dermatol. 2008;158(6):1329-1338.
- Smits, P., Temme, L., and Thien, T. The cardiovascular interaction between caffeine and nicotine in humans. Clin Pharmacol Ther 1993;54(2):194-204. PubMed
- MacKenzie, T., Comi, R., Sluss, P., Keisari, R., Manwar, S., Kim, J., Larson, R., and Baron, J. A. Metabolic and hormonal effects of caffeine: randomized, double-blind, placebo-controlled crossover trial. Metabolism 2007;56(12):1694-1698. PubMed
- Lopez-Garcia, E., Rodriguez-Artalejo, F., Rexrode, K. M., Logroscino, G., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of stroke in women. Circulation 3-3-2009;119(8):1116-1123. PubMed
- Zhang, W., Lopez-Garcia, E., Li, T. Y., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of cardiovascular diseases and all-cause mortality among men with type 2 diabetes. Diabetes Care 2009;32(6):1043-1045. PubMed
- Moisey, L. L., Robinson, L. E., and Graham, T. E. Consumption of caffeinated coffee and a high carbohydrate meal affects postprandial metabolism of a subsequent oral glucose tolerance test in young, healthy males. Br.J Nutr. 2010;103(6):833-841. PubMed
- Chroscinska-Krawczyk, M., Ratnaraj, N., Patsalos, P. N., and Czuczwar, S. J. Effect of caffeine on the anticonvulsant effects of oxcarbazepine, lamotrigine and tiagabine in a mouse model of generalized tonic-clonic seizures. Pharmacol Rep. 2009;61(5):819 PubMed
- Simmonds, M. J., Minahan, C. L., and Sabapathy, S. Caffeine improves supramaximal cycling but not the rate of anaerobic energy release. Eur.J Appl Physiol 2010;109(2):287-295. PubMed
- Buscemi, S., Verga, S., Batsis, J. A., Donatelli, M., Tranchina, M. R., Belmonte, S., Mattina, A., Re, A., and Cerasola, G. Acute effects of coffee on endothelial function in healthy subjects. Eur.J Clin Nutr. 2010;64(5):483-489. PubMed
- Rigato, I., Blarasin, L., and Kette, F. Severe hypokalemia in 2 young bicycle riders due to massive caffeine intake. Clin J Sport Med. 2010;20(2):128-130. PubMed
- Ernest, D., Chia, M., and Corallo, C. E. Profound hypokalaemia due to Nurofen Plus and Red Bull misuse. Crit Care Resusc. 2010;12(2):109-110. DOI
- Conen, D., Chiuve, S. E., Everett, B. M., Zhang, S. M., Buring, J. E., and Albert, C. M. Caffeine consumption and incident atrial fibrillation in women. Am J Clin Nutr 2010;92(3):509-514. PubMed
- Reis, J. P., Loria, C. M., Steffen, L. M., Zhou, X., van, Horn L., Siscovick, D. S., Jacobs, D. R., Jr., and Carr, J. J. Coffee, decaffeinated coffee, caffeine, and tea consumption in young adulthood and atherosclerosis later in life: the CARDIA study. A PubMed
- Clausen, T. Hormonal and pharmacological modification of plasma potassium homeostasis. Fundam.Clin Pharmacol 2010;24(5):595-605. PubMed
- Gronroos, N. N. and Alonso, A. Diet and risk of atrial fibrillation - epidemiologic and clinical evidence -. Circ.J 2010;74(10):2029-2038. PubMed
- Perera, V., Gross, A. S., and McLachlan, A. J. Caffeine and paraxanthine HPLC assay for CYP1A2 phenotype assessment using saliva and plasma. Biomed.Chromatogr. 2010;24(10):1136-1144. PubMed
- Orozco-Gregorio, H., Mota-Rojas, D., Bonilla-Jaime, H., Trujillo-Ortega, M. E., Becerril-Herrera, M., Hernandez-Gonzalez, R., and Villanueva-Garcia, D. Effects of administration of caffeine on metabolic variables in neonatal pigs with peripartum asphyxia PubMed
- Izzo, A. A. and Ernst, E. Interactions between herbal medicines and prescribed drugs: an updated systematic review. Drugs 2009;69(13):1777-1798. PubMed
- Laurie, S. A., Miller, V. A., Grant, S. C., Kris, M. G., and Ng, K. K. Phase I study of green tea extract in patients with advanced lung cancer. Cancer Chemother.Pharmacol. 2005;55(1):33-38. PubMed
- Chiu, A. E., Chan, J. L., Kern, D. G., Kohler, S., Rehmus, W. E., and Kimball, A. B. Double-blinded, placebo-controlled trial of green tea extracts in the clinical and histologic appearance of photoaging skin. Dermatol Surg. 2005;31(7 Pt 2):855-860. PubMed
- Javaid, A. and Bonkovsky, H. L. Hepatotoxicity due to extracts of Chinese green tea (Camellia sinensis): a growing concern. J Hepatol 2006;45(2):334-335. PubMed
- Martinez-Sierra, C., Rendon, Unceta P., and Martin, Herrera L. [Acute hepatitis after green tea ingestion]. Med Clin (Barc.) 6-17-2006;127(3):119.
- Molinari, M., Watt, K. D., Kruszyna, T., Nelson, R., Walsh, M., Huang, W. Y., Nashan, B., and Peltekian, K. Acute liver failure induced by green tea extracts: case report and review of the literature. Liver Transpl. 2006;12(12):1892-1895. PubMed
- Chow, H. H., Hakim, I. A., Vining, D. R., Crowell, J. A., Cordova, C. A., Chew, W. M., Xu, M. J., Hsu, C. H., Ranger-Moore, J., and Alberts, D. S. Effects of repeated green tea catechin administration on human cytochrome P450 activity. Cancer Epidemiol.B PubMed
- Federico, A., Tiso, A., and Loguercio, C. A case of hepatotoxicity caused by green tea. Free Radic.Biol Med 8-1-2007;43(3):474. PubMed
- Sarma, D. N., Barrett, M. L., Chavez, M. L., Gardiner, P., Ko, R., Mahady, G. B., Marles, R. J., Pellicore, L. S., Giancaspro, G. I., and Low, Dog T. Safety of green tea extracts : a systematic review by the US Pharmacopeia. Drug Saf 2008;31(6):469-484. PubMed
- Engdal, S. and Nilsen, O. G. In vitro inhibition of CYP3A4 by herbal remedies frequently used by cancer patients. Phytother.Res. 2009;23(7):906-912.
- Bergman, J. and Schjott, J. Hepatitis caused by Lotus-f3? Basic Clin Pharmacol.Toxicol. 2009;104(5):414-416. PubMed
- Kalus, U., Kiesewetter, H., and Radtke, H. Effect of CYSTUS052 and green tea on subjective symptoms in patients with infection of the upper respiratory tract. Phytother.Res. 2010;24(1):96-100.
- Tatti, S., Stockfleth, E., Beutner, K. R., Tawfik, H., Elsasser, U., Weyrauch, P., and Mescheder, A. Polyphenon E: a new treatment for external anogenital warts. Br.J Dermatol. 2010;162(1):176-184.
- Tsao, A. S., Liu, D., Martin, J., Tang, X. M., Lee, J. J., El-Naggar, A. K., Wistuba, I., Culotta, K. S., Mao, L., Gillenwater, A., Sagesaka, Y. M., Hong, W. K., and Papadimitrakopoulou, V. Phase II randomized, placebo-controlled trial of green tea extra
- Liatsos, G. D., Moulakakis, A., Ketikoglou, I., and Klonari, S. Possible green tea-induced thrombotic thrombocytopenic purpura. Am.J Health Syst.Pharm. 4-1-2010;67(7):531-534. PubMed
- Josic, J., Olsson, A. T., Wickeberg, J., Lindstedt, S., and Hlebowicz, J. Does green tea affect postprandial glucose, insulin and satiety in healthy subjects: a randomized controlled trial. Nutr.J. 2010;9:63. PubMed
- Miller, R. J., Jackson, K. G., Dadd, T., Mayes, A. E., Brown, A. L., and Minihane, A. M. The impact of the catechol-O-methyltransferase genotype on the acute responsiveness of vascular reactivity to a green tea extract. Br.J.Nutr. 2011;105(8):1138-1144.
- Rohde, J., Jacobsen, C., and Kromann-Andersen, H. [Toxic hepatitis triggered by green tea]. Ugeskr.Laeger 1-17-2011;173(3):205-206.
- Tzellos, T. G., Sardeli, C., Lallas, A., Papazisis, G., Chourdakis, M., and Kouvelas, D. Efficacy, safety and tolerability of green tea catechins in the treatment of external anogenital warts: a systematic review and meta-analysis. J.Eur.Acad.Dermatol.Ve PubMed
- Otera, H., Tada, K., Sakurai, T., Hashimoto, K., and Ikeda, A. Hypersensitivity pneumonitis associated with inhalation of catechin-rich green tea extracts. Respiration 2011;82(4):388-392. PubMed
- Yellapu, R. K., Mittal, V., Grewal, P., Fiel, M., and Schiano, T. Acute liver failure caused by 'fat burners' and dietary supplements: a case report and literature review. Can.J.Gastroenterol. 2011;25(3):157-160. PubMed
- Karth, A., Holoshitz, N., Kavinsky, C. J., Trohman, R., and McBride, B. F. A case report of atrial fibrillation potentially induced by hydroxycut: a multicomponent dietary weight loss supplement devoid of sympathomimetic amines. J.Pharm.Pract. 2010;23(3) PubMed
- Hsu, C. H., Liao, Y. L., Lin, S. C., Tsai, T. H., Huang, C. J., and Chou, P. Does supplementation with green tea extract improve insulin resistance in obese type 2 diabetics? A randomized, double-blind, and placebo-controlled clinical trial. Altern.Med.R
- Zheng XX, Xu YL, Li SH, et al. Green tea intake lowers fasting serum total and LDL cholesterol in adults: a meta-analysis of 14 randomized controlled trials. Am.J.Clin.Nutr. 2011;94:601-610. PubMed
- Miller, R. J., Jackson, K. G., Dadd, T., Mayes, A. E., Brown, A. L., Lovegrove, J. A., and Minihane, A. M. The impact of the catechol-O-methyltransferase genotype on vascular function and blood pressure after acute green tea ingestion. Mol.Nutr.Food Res.
- Bogdanski, P., Suliburska, J., Szulinska, M., Stepien, M., Pupek-Musialik, D., and Jablecka, A. Green tea extract reduces blood pressure, inflammatory biomarkers, and oxidative stress and improves parameters associated with insulin resistance in obese, h
- Jurgens, T. M., Whelan, A. M., Killian, L., Doucette, S., Kirk, S., and Foy, E. Green tea for weight loss and weight maintenance in overweight or obese adults. Cochrane.Database.Syst.Rev. 2012;12:CD008650. PubMed
- Sakamoto, O., Saita, N., Yamasaki, H., Tamanoi, M., and Ando, M. Pulmonary granulomatosis caused by aspirated green tea. Chest 1994;106(1):308-309. PubMed
- Jiménez-Encarnación E, Ríos G, Muñoz-Mirabal A, Vilá LM. Euforia-induced acute hepatitis in a patient with scleroderma. BMJ Case Rep 2012;2012. PubMed
- Choi JS, Burm JP. Effects of oral epigallocatechin gallate on the pharmacokinetics of nicardipine in rats. Arch Pharm Res. 2009 Dec;32(12):1721-5. PubMed
- Chung JH, Choi DH, Choi JS. Effects of oral epigallocatechin gallate on the oral pharmacokinetics of verapamil in rats. Biopharm Drug Dispos. 2009 Mar;30(2):90-3. PubMed
- Crew KD, Brown P, Greenlee H, Bevers TB, Arun B, Hudis C, McArthur HL, Chang J, Rimawi M, Vornik L, Cornelison TL, Wang A, Hibshoosh H, Ahmed A, Terry MB, Santella RM, Lippman SM, Hershman DL. Phase IB randomized, double-blinded, placebo-controlled, dose
- Dryden GW, Lam A, Beatty K, Qazzaz HH, McClain CJ. A pilot study to evaluate the safety and efficacy of an oral dose of (-)-epigallocatechin-3-gallate-rich polyphenon E in patients with mild to moderate ulcerative colitis. Inflamm Bowel Dis. 2013 Aug;19(9 PubMed
- Gallo E, Maggini V, Berardi M, Pugi A, Notaro R, Talini G, Vannozzi G, Bagnoli S, Forte P, Mugelli A, Annese V, Firenzuoli F, Vannacci A. Is green tea a potential trigger for autoimmune hepatitis? Phytomedicine. 2013 Oct 15;20(13):1186-9. PubMed
- Liu K, Zhou R, Wang B, Chen K, Shi LY, Zhu JD, Mi MT. Effect of green tea on glucose control and insulin sensitivity: a meta-analysis of 17 randomized controlled trials. Am J Clin Nutr. 2013 Aug;98(2):340-8. PubMed
- Onakpoya I, Spencer E, Heneghan C, Thompson M. The effect of green tea on blood pressure and lipid profile: a systematic review and meta-analysis of randomized clinical trials. Nutr Metab Cardiovasc Dis. 2014 Aug;24:823-36. PubMed
- Patel SS, Beer S, Kearney DL, Phillips G, Carter BA. Green tea extract: a potential cause of acute liver failure. World J Gastroenterol. 2013 Aug 21;19(31):5174-7. PubMed
- Pillukat MH, Bester C, Hensel A, Lechtenberg M, Petereit F, Beckebaum S, Müller KM, Schmidt HH. Concentrated green tea extract induces severe acute hepatitis in a 63-year-old woman--a case report with pharmaceutical analysis. J Ethnopharmacol. 2014 Aug 8; PubMed
- Schönthal AH. Adverse effects of concentrated green tea extracts. Mol Nutr Food Res. 2011 Jun;55(6):874-85. PubMed
- Shiraishi M, Haruna M, Matsuzaki M, Ota E, Murayama R, Murashima S. Association between the serum folate levels and tea consumption during pregnancy. Biosci Trends. 2010 Oct;4(5):225-30.
- Jang EH, Choi JY, Park CS, Lee SK, Kim CE, Park HJ, Kang JS, Lee JW, Kang JH. Effects of green tea extract administration on the pharmacokinetics of clozapine in rats. J Pharm Pharmacol. 2005 Mar;57(3):311-6. PubMed
- Trudel D, Labbé DP, Araya-Farias M, Doyen A, Bazinet L, Duchesne T, Plante M, Grégoire J, Renaud MC, Bachvarov D, Têtu B, Bairati I. A two-stage, single-arm, phase II study of EGCG-enriched green tea drink as a maintenance therapy in women with advanced s
- Zheng XX, Xu YL, Li SH, Hui R, Wu YJ, Huang XH. Effects of green tea catechins with or without caffeine on glycemic control in adults: a meta-analysis of randomized controlled trials. Am J Clin Nutr. 2013 Apr;97(4):750-62. PubMed
- Caldeira D, Martins C, Alves LB, Pereira H, Ferreira JJ, Costa J. Caffeine does not increase the risk of atrial fibrillation: a systematic review and meta-analysis of observational studies. Heart. 2013;99(19):1383-9. doi: 10.1136/heartjnl-2013-303950. Re PubMed
- Cheng M, Hu Z, Lu X, Huang J, Gu D. Caffeine intake and atrial fibrillation incidence: dose response meta-analysis of prospective cohort studies. Can J Cardiol. 2014 Apr;30(4):448-54. doi: 10.1016/j.cjca.2013.12.026. Epub 2014 2. Review. PubMed
- van der Hoeven N, Visser I, Schene A, van den Born BJ. Severe hypertension related to caffeinated coffee and tranylcypromine: a case report. Ann Intern Med. 2014 May 6;160(9):657-8. doi: 10.7326/L14-5009-8. No abstract available. PubMed
- Dixit S, Stein PK, Dewland TA, Dukes JW, Vittinghoff E, Heckbert SR, Marcus GM. Consumption of Caffeinated Products and Cardiac Ectopy. J Am Heart Assoc. 2016 26;5(1). pii: e002503. doi: 10.1161/JAHA.115.002503. PubMed
- Health Canada. Health Product Info Watch. October 2016; 5-6. Available at: http://www.hc-sc.gc.ca/dhp-mps/medeff/bulletin/hpiw-ivps_2016-10-eng.php#a15.
- Green Tea Extract-Containing Natural Health Products - Rare Risk of Serious Liver Injury. Recalls & alerts. November 15, 2017. http://healthycanadians.gc.ca/recall-alert-rappel-avis/hc-sc/2017/65100a-eng.php. Accessed November 10, 2017.
- Mazzanti G, Di Sotto A, Vitalone A. Hepatotoxicity of green tea: an update. Arch Toxicol. 2015;89(8):1175-91. PubMed
- Isomura T, Suzuki S, Origasa H, et al. Liver-related safety assessment of green tea extracts in humans: a systematic review of randomized controlled trials. Eur J Clin Nutr. 2016;70(11):1221-1229. PubMed
- Drug Record: Green Tea (Camellia Sinesis). LiverTox: National Institutes of Health, U.S. Department of Health & Human Services, March 2014. https://livertox.nlm.nih.gov//GreenTea.htm. Accessed November 20, 2017.
- Yates AA, Erdman JW Jr, Shao A, Dolan LC, Griffiths JC. Bioactive nutrients - Time for tolerable upper intake levels to address safety. Regul Toxicol Pharmacol. 2017;84:94-101. PubMed
- Younes M, Aggett P, Aguilar F, et al. EFSA Panel on Food Additives and Nutrient Sources added to Food (ANS). Scientific opinion on the safety of green tea catechins. EFSA Journal 2018;16(4):5239. PubMed
- Zuchinali P, Riberio PA, Pimentel M, da Rosa PR, Zimerman LI, Rohde LE. Effect of caffeine on ventricular arrhythmia: a systematic review and meta-analysis of experimental and clinical studies. Europace 2016 Feb;18(2):257-66. PubMed
- Dostal AM, Samavat H, Bedell S, et al. The safety of green tea extract supplementation in postmenopausal women at risk for breast cancer: results of the Minnesota Green Tea Trial. Food Chem Toxicol. 2015 Sep;83:26-35. PubMed
- Shamekhi Z, Amani R, Habibagahi Z, Namjoyan F, Ghadiri A, Saki Malehi A. A Randomized, Double-blind, Placebo-controlled Clinical Trial Examining the Effects of Green Tea Extract on Systemic Lupus Erythematosus Disease Activity and Quality of Life. Phytoth PubMed
- Lagier D, Nee L, Guieu R, et al. Peri-operative oral caffeine does not prevent postoperative atrial fibrillation after heart valve surgery with cardiopulmonary bypass: a randomized controlled clinical trial. Eur J Anaesthesiol. 2018 Apr 26. [Epub ahead of DOI
- Voskoboinik A, Kalman JM, Kistler PM. Caffeine and arrhythmias: time to grind the data. JACC: Clin Electrophysiol. 2018;4(4):425-32. PubMed
- Chong SJ, Howard KA, Knox C. Hypokalaemia and drinking green tea: a literature review and report of 2 cases. BMJ Case Rep. 2016;2016. pii: bcr2016214425. PubMed
- Qiao J, Gu C, Shang W, et al. Effect of green tea on pharmacokinetics of 5-fluorouracil in rats and pharmacodynamics in human cell lines in vitro. Food Chem Toxicol. 2011;49(6):1410-5. PubMed
- Abe O, Ono T, Sato H, et al. Role of (-)-epigallocatechin gallate in the pharmacokinetic interaction between nadolol and green tea in healthy volunteers. Eur J Clin Pharmacol 2018;74(6):775-83. doi: 10.1007/s00228-018-2436-2. PubMed
- Wikoff D, Welsh BT, Henderson R, et al. Systematic review of the potential adverse effects of caffeine consumption in healthy adults, pregnant women, adolescents, and children. Food Chem Toxicol 2017;109:585-648. PubMed
- Nutescu EA, Shapiro NL, Ibrahim S, et al. Warfarin and its interactions with foods, herbs and other dietary supplements. Expert Opin Drug Saf. 2006;5(3):433-51. PubMed
- Abdelkawy KS, Abdelaziz RM, Abdelmageed AM, Donia AM, El-Khodary NM. Effects of green tea extract on atorvastatin pharmacokinetics in healthy volunteers. Eur J Drug Metab Pharmacokinet. 2020;45(3):351-360. PubMed
- Filippini T, Malavolti M, Borrelli F, et al. Green tea (Camellia sinensis) for the prevention of cancer. Cochrane Database Syst Rev. 2020;3(3):CD005004. PubMed
- Huang S, Xu Q, Liu L, et al. Effect of green tea and (-)-epigallocatechin gallate on the pharmacokinetics of rosuvastatin. Curr Drug Metab. 2020. PubMed
- Mahmoodi M, Hosseini R, Kazemi A, Ofori-Asenso R, Mazidi M, Mazloomi SM. Effects of green tea or green tea catechin on liver enzymes in healthy individuals and people with nonalcoholic fatty liver disease: A systematic review and meta-analysis of randomiz
- Misaka S, Abe O, Ono T, et al. Effects of single green tea ingestion on pharmacokinetics of nadolol in healthy volunteers. Br J Clin Pharmacol. 2020. PubMed
- Oketch-Rabah HA, Roe AL, Rider CV, et al. United States Pharmacopeia (USP) comprehensive review of the hepatotoxicity of green tea extracts. Toxicol Rep. 2020;7:386-402. PubMed
- Kim TE, Ha N, Kim Y, et al. Effect of epigallocatechin-3-gallate, major ingredient of green tea, on the pharmacokinetics of rosuvastatin in healthy volunteers. Drug Des Devel Ther. 2017;11:1409-1416. PubMed
- Misaka S, Ono Y, Uchida A, et al. Impact of green tea catechin ingestion on the pharmacokinetics of lisinopril in healthy volunteers. Clin Transl Sci. 2020. PubMed
- Darweesh RS, El-Elimat T, Zayed A, et al. The effect of grape seed and green tea extracts on the pharmacokinetics of imatinib and its main metabolite, N-desmethyl imatinib, in rats. BMC Pharmacol Toxicol. 2020;21(1):77. PubMed
- Sonoda J, Ogata K, Yoshikawa N, Sato K, Ikeda R, Shimodozono Y. Impact of green tea intake on the pharmacokinetics of celiprolol in healthy subjects. Int J Clin Pharmacol Ther. 2020. PubMed
- Kim S, Park TH, Kim WI, Park S, Kim JH, Cho MK. The effects of green tea on acne vulgaris: A systematic review and meta-analysis of randomized clinical trials. Phytother Res. 2021;35(1):374-383. PubMed
- Percevault S, Charpiat B, Lebossé F, Mabrut JY, Vial T, Colom M. Green tea and hepatoxicity: Two case reports. Therapie 2021. PubMed
- Kajita N, Miyama S, Kinoshita K, Yoshida K, Narita M. Green tea-induced anaphylaxis: The first pediatric case report. Allergol Int 2021;70(4):507-508. PubMed
- Zheng KH, Zhu K, Wactawski-Wende J, et al. Caffeine intake from coffee and tea and invasive breast cancer incidence among postmenopausal women in the Women's Health Initiative. Int J Cancer 2021;149(12):2032-2044. PubMed
- Wang S, Li X, Yang Y, et al. Does coffee, tea and caffeine consumption reduce the risk of incident breast cancer? A systematic review and network meta-analysis. Public Health Nutr 2021;24(18):6377-6389. PubMed
- Alshabi AM, Alkahtani SA, Shaikh IA, Habeeb MS. Caffeine modulates pharmacokinetic and pharmacodynamic profiles of pioglitazone in diabetic rats: Impact on therapeutics. Saudi Med J 2021;42(2):151-160. PubMed
- Gleason JL, Sundaram R, Mitro SD, et al. Association of maternal caffeine consumption during pregnancy with child growth. JAMA Netw Open. 2022;5(10):e2239609. PubMed
- Seufferlein T, Ettrich TJ, Menzler S, et al. Green tea extract to prevent colorectal adenomas, results of a randomized, placebo-controlled clinical trial. Am J Gastroenterol 2022;117(6):884-894. PubMed
- Teramoto M, Yamagishi K, Muraki I, Tamakoshi A, Iso H. Coffee and green tea consumption and cardiovascular disease mortality among people with and without hypertension. J Am Heart Assoc 2023;12(2):e026477. PubMed
- Veerman GDM, van der Werff SC, Koolen SLW, et al. The influence of green tea extract on nintedanib's bioavailability in patients with pulmonary fibrosis. Biomed Pharmacother 2022;151:113101. PubMed
- Misaka S, Ono Y, Taudte RV, et al. Exposure of fexofenadine, but not pseudoephedrine, is markedly decreased by green tea extract in healthy volunteers. Clin Pharmacol Ther 2022;112(3):627-634. PubMed
- Zhao H, Zhu W, Zhao X, et al. Efficacy of epigallocatechin-3-gallate in preventing dermatitis in patients with breast cancer receiving postoperative radiotherapy: A double-blind, placebo-controlled, phase 2 randomized clinical trial. JAMA Dermatol 2022;15 PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
Bacopa 12 references
- Stough C, Lloyd J, Clarke J, et al. The chronic effects of an extract of Bacopa monniera (Brahmi) on cognitive function in healthy human subjects. Psychopharmacology 2001;156:481-4..
- Yadav SK, Jain AK, Tripathi SN, Gupta JP. Irritable bowel syndrome: therapeutic evaluation of indigenous drugs. Indian J Med Res 1989;90:496-503..
- Morgan A, Stevens J. Does Bacopa monnieri improve memory performance in older persons? Results of a randomized, placebo-controlled, double-blind trial. J Altern Complement Med 2010;16:753-9.
- Kar, A., Panda, S., and Bharti, S. Relative efficacy of three medicinal plant extracts in the alteration of thyroid hormone concentrations in male mice. J Ethnopharmacol. 2002;81(2):281-285. PubMed
- Mukherjee, G. D. and Dey, C. D. Clinical trial on Brahmi. I. J.Exp.Med.Sci. 1966;10(1):5-11.
- Kar A, Pandit S, Mukherjee K, Bahadur S, Mukherjee PK. Safety assessment of selected medicinal food plants used in Ayurveda through CYP450 enzyme inhibition study. J Sci Food Agric 2017;97(1):333-40. doi: 10.1002/jsfa.7739. PubMed
- Kongkeaw C, Dilokthornsakul P, Thanarangsarit P, et al. Meta-analysis of randomized controlled trials on cognitive effects of Bacopa monnieri extract. J Ethnopharmacol 2014;151(1):528-35. PubMed
- Ramasamy S, Kiew LV, Chung LY. Inhibition of human cytochrome P450 enzymes by Bacopa monnieri standardized extract and constituents. Molecules 2014;19(2):2588-601. PubMed
- Prabhakar S, Vishnu VY, Modi M, et al. Efficacy of Bacopa monnieri (Brahmi) and donepezil in Alzheimer's disease and mild cognitive impairment: a randomized double-blind parallel phase 2b study. Ann Indian Acad Neurol 2020;23(6):767-73. PubMed
- Acquarulo B, Tandon P, Macica CM. Suspected cholinergic toxicity due to cevimeline hydrochloride and Bacopa monnieri interaction: a case report. J Med Case Rep 2022;16(1):253. PubMed
- Keegan AP, Stough C, Paris D, et al. Bacopa monnieri supplementation has no effect on serum brain-derived neurotrophic factor levels but beneficially modulates nuclear factor kappa B and cyclic AMP response element-binding protein levels in healthy elderl
- Yaworski AM, Blyumin M, Chang T, Mammen AL, Greene M. Necrotizing myopathy with elevated anti-HMGCR antibodies following exposure to the supplement Bacopa. Muscle Nerve 2023;67(2):E1-E3.
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC