
Optihear Ingredients & Drug Interactions
by SuperSmart
What is this page for?
First and foremost: checking Optihear against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Optihear is a dietary supplement by SuperSmart with 7 active ingredients. Its ingredients are commonly taken for bone health and osteoporosis, correcting vitamin d deficiency, immune system support.Based on those ingredients, 1,630 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Ginkgo biloba Leaf Extract, Quercetin, Vitamin B3. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Optihear by SuperSmart
Ask about any prescription or over-the-counter medication and we check it for interactions with Optihear by SuperSmart — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Optihear by SuperSmart
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
Optihear contains 7 active ingredients. Vitamin D3 supports bone health and calcium absorption.
Zinc aids immune function and tissue repair. Vitamin B3 is included for metabolic support, though we hold no detailed data on it.
Ginkgo biloba leaf extract is used traditionally for circulation and cognitive support. Magnesium supports muscle and nerve function.
Quercetin is a plant compound with antioxidant properties. Vitamin A supports vision and immune health.
The capsule also contains two inactive ingredients — acacia gum and white rice flour — which serve as fillers and binders.
Does it work?
Moderate evidence
Vitamin D3 is effective for treating vitamin D deficiency-related bone disorders, including rickets, osteomalacia, renal bone disease, and low blood calcium (hypoparathyroidism). Zinc is effective for zinc deficiency and likely effective for Wilson disease (a copper storage disorder); it may help with acne and age-related vision loss, though evidence is less certain.
Ginkgo biloba has possibly effective evidence for hearing loss, stroke recovery, schizophrenia, premenstrual syndrome, dementia, and anxiety — the evidence is suggestive but not definitive. Magnesium is effective for indigestion and constipation.
Quercetin's effectiveness for various conditions is not yet reliably established in the data we hold. Vitamin A is effective for vitamin A deficiency and possibly effective for measles, skin aging, and certain intestinal conditions.
How safe is it?
Well-documented data
At recommended doses, these ingredients are generally well tolerated. Vitamin D3 is safe in normal amounts but can cause toxicity at very high doses, with symptoms like high blood calcium levels (hypercalcemia).
Zinc is well tolerated below 40 mg daily; higher doses can cause nausea, diarrhea, and metallic taste, and very high long-term use may deplete copper. Ginkgo is generally well tolerated for up to 6 years but may increase bleeding risk and has rare reports of heart rhythm problems.
Magnesium commonly causes diarrhea and stomach upset at higher doses. Quercetin at typical supplement amounts is generally well tolerated; high doses and long-term safety are not well studied.
Vitamin A is safe at recommended levels but accumulates in the body — high doses can cause liver damage, headaches, and skin problems.
Meds to double-check
Major interaction found
Before taking Optihear, double-check these medication types with your pharmacist: retinoid skin medications (vitamin A interaction is major), blood pressure and heart rhythm drugs (vitamin D3, magnesium, ginkgo), blood thinners like warfarin (ginkgo, quercetin, vitamin A), Parkinson's disease medications (magnesium), antibiotics including quinolones, tetracyclines, and cephalexin (zinc, magnesium, quercetin), cholesterol medications (vitamin D3, ginkgo, quercetin), HIV drugs (ginkgo, zinc), diabetes medications (magnesium), and any potentially liver-damaging drugs (vitamin A). These are the main categories where documented interactions exist.
The bottom line
Scorecard at a glanceFully disclosed formula with some supporting evidence for its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
Optihear may be worth considering if you're looking for nutritional support for hearing, vision, and general wellness — but it's not a treatment for hearing loss itself. If you take any prescription medications, especially heart drugs, blood thinners, antibiotics, cholesterol medications, or HIV treatments, check your specific medications with the tool below before starting.
Talk with your pharmacist or doctor about whether this product fits your health situation.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 7 of 7 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jun 25, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Optihear, straight from the product label.
| Brand | SuperSmart |
|---|---|
| Barcode (UPC) | 5453003820444 |
| Net contents | 120 Vegetarian Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Jun 25, 2025 |
| DSLD ID | 332471 |
| Product type | Other Combinations |
| Supplement form | Capsule |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
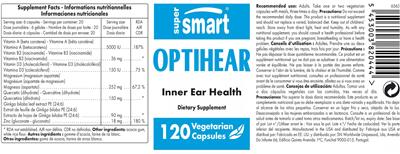
Supplement Facts
The label details for Optihear by SuperSmart, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Vitamin D3 | 150 IU | 75% |
| Zinc | 18 mg | 180% |
| Vitamin B3 | 36 mg | -- |
| Ginkgo biloba Leaf Extract | 90 mg | -- |
| Magnesium | 252 mg | 67.2% |
| Quercetin | 150 mg | -- |
| Vitamin A | 5000 IU | 187% |
Other ingredients: Acacia Gum, White Rice Flour
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formulation
Inner ear health
FDA Statement of Identity
Dietary Supplement
Suggested/Recommended/Usage/Directions
Recommended use: Adults. Take one or two vegetarian capsules with meals, three times a day.
Precautions
Precautions: Do not exceed the recommended daily dose. This product is a nutritional supplement and should not replace a varied, balanced diet.
Keep out of childrens' reach.
As with any nutritional supplement, you should consult a health professional before taking this product if you are pregnant, breastfeeding or have a health problem.
Storage
Store away from direct light, heat and humidity.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Optihear by SuperSmart label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Optihear by SuperSmart
These are the 7 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Capsule(s) Dosage formCapsule Servings per container20 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Vitamin D3
Interacts with715 drugs
Vitamin D is a fat-soluble vitamin that helps your body absorb calcium and is important for healthy bones, muscles, and immune function. Many people,...
Vitamin D3 monograph & interactionsZinc
Interacts with67 drugs
Zinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but suppleme...
Zinc monograph & interactionsVitamin B3
Interacts with727 drugs
Niacin (vitamin B3) is an essential nutrient your body needs for energy and metabolism, and deficiency is uncommon in most developed countries. Prescr...
Vitamin B3 monograph & interactionsGinkgo biloba Leaf Extract
Interacts with1,266 drugs
Ginkgo is one of the world's most popular herbal supplements, mostly taken to support memory and circulation. The evidence for these uses is mixed and...
Ginkgo biloba Leaf Extract monograph & interactionsMagnesium
Interacts with295 drugs
Magnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preven...
Magnesium monograph & interactionsQuercetin
Interacts with1,169 drugs
Quercetin is a plant flavonoid with antioxidant and anti-inflammatory properties found in many common foods and sold as a supplement. While early rese...
Quercetin monograph & interactionsVitamin A
Interacts with387 drugs
Vitamin A is an essential nutrient important for vision, skin, immune function, and growth. Most people get enough from a balanced diet, and supplemen...
Vitamin A monograph & interactionsOther (inactive) ingredients: Acacia Gum, White Rice Flour. These complete the product’s ingredient list but are not active constituents.
Optihear by SuperSmart Drug Interactions
HelloPharmacist Interaction Report
Optihear by SuperSmart contains several ingredients with documented interactions with medications.
The most serious concern is vitamin A, which can cause major interactions with retinoids (vitamin A derivatives used for skin conditions) — combining them risks dangerously high vitamin A levels in your body.
Read the full breakdown — every affected drug type, severity by severity
Several ingredients have moderate interactions with common drug types. Vitamin D3 interacts with thiazide water pills, heart rhythm medications (verapamil, diltiazem), cholesterol drugs (atorvastatin), the heart medication digoxin, and the psoriasis treatment calcipotriene — all related to a potential buildup of calcium in your blood.
Magnesium reduces how your body absorbs levodopa (used for Parkinson's disease) by up to 35%, and also affects muscle relaxants, certain diuretics, blood pressure medications, diabetes drugs, and some antibiotics. Ginkgo biloba has a major interaction with talinolol (a beta-blocker), and moderate interactions with cholesterol and anxiety medications, blood thinners, and HIV drugs.
Zinc interferes with several antibiotics (quinolones, tetracyclines, cephalexin), a copper-binding drug (penicillamine), and HIV medications (ritonavir, integrase inhibitors). Quercetin theoretically affects blood pressure medication (losartan), cholesterol drugs, blood thinners, and certain antibiotics.
We could not check vitamin B3 — no data is on file for it.
Altogether, these interactions span 1,587 individual medications. Check your exact medications with the search tool on this page before starting Optihear.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Optihear?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Optihear interact with 1,630 drugs. Click any drug to see the details.
7 of the 7 ingredients in Optihear interact with drugs. Each result below shows which ingredient is responsible. Ginkgo biloba Leaf Extract Quercetin Vitamin B3 Vitamin D3 Vitamin A Magnesium Zinc
Acetaminophen, PseudoephedrineChildren's Tylenol Sinus, Dristan N.D., Non-Aspirin Sinus, Ornex, Ornex-Max, Sinutab +5 more
How Acetaminophen, Pseudoephedrine interacts with Optihear — through 3 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Pseudoephedrine interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Pseudoephedrine interactionGinkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Pseudoephedrine interactionAcetaminophen, Pseudoephedrine, TriprolidineActifed Plus ES
How Acetaminophen, Pseudoephedrine, Triprolidine interacts with Optihear — through 3 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Pseudoephedrine, Triprolidine interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Pseudoephedrine, Triprolidine interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Pseudoephedrine, Triprolidine interactionAcetazolamideAk-Zol, Diamox
How Acetazolamide interacts with Optihear — through 3 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractAnticonvulsants Moderate
Interaction Summary
Theoretically, ginkgo might reduce the effectiveness of anticonvulsants.
Read the full Ginkgo Biloba Leaf Extract + Acetazolamide interactionVitamin B3Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
Read the full Vitamin B3 + Acetazolamide interactionQuercetinAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking quercetin with antihypertensive drugs might increase the risk of hypotension.
Read the full Quercetin + Acetazolamide interactionAcetohexamideDymelor
How Acetohexamide interacts with Optihear — through 5 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetohexamide interactionMagnesiumSulfonylureas Moderate
Interaction Summary
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Read the full Magnesium + Acetohexamide interactionQuercetinAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, concomitant use of quercetin and antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Quercetin + Acetohexamide interactionGinkgo Biloba Leaf ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking ginkgo with antidiabetes drugs might alter the response to antidiabetes drugs.
Read the full Ginkgo Biloba Leaf Extract + Acetohexamide interactionVitamin B3Antidiabetes Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Niacin can increase blood glucose levels and may diminish the effects of antidiabetes drugs.
Read the full Vitamin B3 + Acetohexamide interactionAcetylsalicylic AcidEntrophen
How Acetylsalicylic Acid interacts with Optihear — through 4 ingredients. Tap an ingredient for the detail:
Vitamin B3Anticoagulant/antiplatelet Drugs, Aspirin Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Vitamin B3 + Acetylsalicylic Acid interactionGinkgo Biloba Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin.
Read the full Ginkgo Biloba Leaf Extract + Acetylsalicylic Acid interactionQuercetinOrganic Anion Transporter 3 (oat3) Substrates, Organic Anion Transporter 1 (oat1) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the effects and adverse effects of OAT3 substrates.
Read the full Quercetin + Acetylsalicylic Acid interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Acetylsalicylic Acid interactionAcyclovirAvaclyr, Sitavig, Zovirax, Zovirax Injection
How Acyclovir interacts with Optihear — through 2 ingredients. Tap an ingredient for the detail:
QuercetinOrganic Anion Transporter 1 (oat1) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the effects and adverse effects of OAT1 substrates.
Read the full Quercetin + Acyclovir interactionGinkgo Biloba Leaf ExtractSeizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Biloba Leaf Extract + Acyclovir interactionAdagrasibKrazati
How Adagrasib interacts with Optihear — through 5 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Adagrasib interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Adagrasib interactionGinkgo Biloba Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Biloba Leaf Extract + Adagrasib interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Adagrasib interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Adagrasib interactionAdefovirHepsera
How Adefovir interacts with Optihear — through 1 ingredient. Tap an ingredient for the detail:
QuercetinOrganic Anion Transporter 1 (oat1) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the effects and adverse effects of OAT1 substrates.
Read the full Quercetin + Adefovir interactionAerosphere Budesonide, Formoterol Fumarate, GlycopyrrolateBreztri
How Aerosphere Budesonide, Formoterol Fumarate, Glycopyrrolate interacts with Optihear — through 2 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractCytochrome P450 2c9 (cyp2c9) Substrates, Cytochrome P450 2c19 (cyp2c19) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP2C9.
Read the full Ginkgo Biloba Leaf Extract + Aerosphere Budesonide, Formoterol Fumarate, Glycopyrrolate interactionQuercetinCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 2c9 (cyp2c9) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Quercetin + Aerosphere Budesonide, Formoterol Fumarate, Glycopyrrolate interactionAfatinib DimaleateGilotrif
How Afatinib Dimaleate interacts with Optihear — through 2 ingredients. Tap an ingredient for the detail:
QuercetinP-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of P-glycoprotein substrates.
Read the full Quercetin + Afatinib Dimaleate interactionGinkgo Biloba Leaf ExtractP-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, taking ginkgo with P-glycoprotein substrates might increase the levels and adverse effects of these substrates.
Read the full Ginkgo Biloba Leaf Extract + Afatinib Dimaleate interactionAgomelatineValdoxan
How Agomelatine interacts with Optihear — through 2 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractCytochrome P450 2c19 (cyp2c19) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP2C19.
Read the full Ginkgo Biloba Leaf Extract + Agomelatine interactionQuercetinCytochrome P450 2c9 (cyp2c9) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2C9 substrates.
Read the full Quercetin + Agomelatine interactionAlbiglutideTanzeum
How Albiglutide interacts with Optihear — through 3 ingredients. Tap an ingredient for the detail:
Vitamin B3Antidiabetes Drugs Moderate
Interaction Summary
Niacin can increase blood glucose levels and may diminish the effects of antidiabetes drugs.
Read the full Vitamin B3 + Albiglutide interactionGinkgo Biloba Leaf ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking ginkgo with antidiabetes drugs might alter the response to antidiabetes drugs.
Read the full Ginkgo Biloba Leaf Extract + Albiglutide interactionQuercetinAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, concomitant use of quercetin and antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Quercetin + Albiglutide interactionAlcuroniumAlcuronium
How Alcuronium interacts with Optihear — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Alcuronium interactionAldesleukinProleukin
How Aldesleukin interacts with Optihear — through 2 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Aldesleukin interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Aldesleukin interactionAlectinib HydrochlorideAlecensa
How Alectinib Hydrochloride interacts with Optihear — through 2 ingredients. Tap an ingredient for the detail:
Vitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Alectinib Hydrochloride interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Alectinib Hydrochloride interactionAlendronateBinosto, Fosamax
How Alendronate interacts with Optihear — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumBisphosphonates Moderate
Interaction Summary
Magnesium can decrease absorption of bisphosphonates.
Read the full Magnesium + Alendronate interactionAlendronate Sodium
How Alendronate Sodium interacts with Optihear — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumBisphosphonates Moderate
Interaction Summary
Magnesium can decrease absorption of bisphosphonates.
Read the full Magnesium + Alendronate Sodium interactionAlendronate Sodium, CholecalciferolFosamax Plus D
How Alendronate Sodium, Cholecalciferol interacts with Optihear — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumBisphosphonates Moderate
Interaction Summary
Magnesium can decrease absorption of bisphosphonates.
Read the full Magnesium + Alendronate Sodium, Cholecalciferol interactionAlfentanilAlfenta
How Alfentanil interacts with Optihear — through 3 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractSeizure Threshold Lowering Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Biloba Leaf Extract + Alfentanil interactionQuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Alfentanil interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Alfentanil interactionAlfuzosinUroxatral
How Alfuzosin interacts with Optihear — through 3 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Alfuzosin interactionGinkgo Biloba Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Biloba Leaf Extract + Alfuzosin interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Alfuzosin interactionAlginic Acid, Aluminum HydroxideRafton
How Alginic Acid, Aluminum Hydroxide interacts with Optihear — through 2 ingredients. Tap an ingredient for the detail:
MagnesiumAntacids Moderate
Interaction Summary
Use of acid reducers may reduce the laxative effect of magnesium oxide.
Read the full Magnesium + Alginic Acid, Aluminum Hydroxide interactionVitamin D3Aluminum Moderate
Interaction Summary
Vitamin D might increase aluminum absorption and toxicity, but this has only been reported in people with renal failure.
Read the full Vitamin D3 + Alginic Acid, Aluminum Hydroxide interactionAliskirenTekturna
How Aliskiren interacts with Optihear — through 4 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Biloba Leaf Extract + Aliskiren interactionQuercetinCytochrome P450 3a4 (cyp3a4) Substrates, Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Aliskiren interactionVitamin B3Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
Read the full Vitamin B3 + Aliskiren interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Aliskiren interactionAllopurinolCaplenal, Cosuric, Rimapurinol, Zyloprim, Zyloric
How Allopurinol interacts with Optihear — through 2 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Allopurinol interactionVitamin B3Hepatotoxic Drugs, Allopurinol (zyloprim) Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Allopurinol interactionAlmotriptanAlmogran, Axert
How Almotriptan interacts with Optihear — through 3 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Biloba Leaf Extract + Almotriptan interactionQuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Almotriptan interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Almotriptan interactionAlogliptinNesina
How Alogliptin interacts with Optihear — through 5 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates, Antidiabetes Drugs +1 Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Alogliptin interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Alogliptin interactionVitamin B3Antidiabetes Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Niacin can increase blood glucose levels and may diminish the effects of antidiabetes drugs.
Read the full Vitamin B3 + Alogliptin interactionGinkgo Biloba Leaf ExtractAntidiabetes Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, taking ginkgo with antidiabetes drugs might alter the response to antidiabetes drugs.
Read the full Ginkgo Biloba Leaf Extract + Alogliptin interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Alogliptin interactionAlogliptin, MetforminKazano
How Alogliptin, Metformin interacts with Optihear — through 3 ingredients. Tap an ingredient for the detail:
QuercetinAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, concomitant use of quercetin and antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Quercetin + Alogliptin, Metformin interactionVitamin B3Antidiabetes Drugs Moderate
Interaction Summary
Niacin can increase blood glucose levels and may diminish the effects of antidiabetes drugs.
Read the full Vitamin B3 + Alogliptin, Metformin interactionGinkgo Biloba Leaf ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking ginkgo with antidiabetes drugs might alter the response to antidiabetes drugs.
Read the full Ginkgo Biloba Leaf Extract + Alogliptin, Metformin interactionAlogliptin, PioglitazoneOseni
How Alogliptin, Pioglitazone interacts with Optihear — through 5 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractAntidiabetes Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, taking ginkgo with antidiabetes drugs might alter the response to antidiabetes drugs.
Read the full Ginkgo Biloba Leaf Extract + Alogliptin, Pioglitazone interactionVitamin B3Hepatotoxic Drugs, Antidiabetes Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Alogliptin, Pioglitazone interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Alogliptin, Pioglitazone interactionQuercetinCytochrome P450 3a4 (cyp3a4) Substrates, Antidiabetes Drugs +1 Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Alogliptin, Pioglitazone interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Alogliptin, Pioglitazone interactionAlpelisibPiqray
How Alpelisib interacts with Optihear — through 3 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Biloba Leaf Extract + Alpelisib interactionQuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Alpelisib interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Alpelisib interactionAlprazolamNiravam, Xanax
How Alprazolam interacts with Optihear — through 3 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Alprazolam interactionGinkgo Biloba Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Alprazolam (xanax) Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Biloba Leaf Extract + Alprazolam interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Alprazolam interactionAlteplase, TpaActilyse, Activase
How Alteplase, Tpa interacts with Optihear — through 3 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin.
Read the full Ginkgo Biloba Leaf Extract + Alteplase, Tpa interactionVitamin B3Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Vitamin B3 + Alteplase, Tpa interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Alteplase, Tpa interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Optihear with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Ginkgo biloba Leaf Extract
Talinolol
Taking ginkgo with talinolol seems to increase blood levels of talinolol.
There is some evidence that using ginkgo leaf extract 120 mg orally three times daily for 14 days can increase levels of talinolol by 36% in healthy male individuals. However, single doses of ginkgo do not seem to affect talinolol pharmacokinetics.
Alprazolam (Xanax)
Theoretically, ginkgo might decrease the levels and clinical effects of alprazolam.
In clinical research, ginkgo extract (Ginkgold) 120 mg twice daily seems to decrease alprazolam levels by about 17%. However, ginkgo does not appear to decrease the elimination half-life of alprazolam. This suggests that ginkgo is more likely to decrease absorption of alprazolam rather than induce hepatic metabolism of alprazolam.
Anticoagulant/Antiplatelet Drugs
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin. Theoretically, ginkgo might increase the risk of bleeding if used with other anticoagulant or antiplatelet drugs.
Several pharmacodynamic studies suggest that ginkgo inhibits platelet aggregation. It is thought that the ginkgo constituent, ginkgolide B, displaces platelet-activating factor (PAF) from its binding sites, decreasing blood coagulation. Several case reports have documented serious bleeding events in patients taking ginkgo. However, population and clinical studies have produced mixed results. Some evidence shows that short-term use of ginkgo leaf does not significantly reduce platelet aggregation and blood clotting. A study in healthy males who took a specific ginkgo leaf extract (EGb 761) 160 mg twice daily for 7 days found no change in prothrombin time. An analysis of a large medical record database suggests that ginkgo increases the risk of a bleeding adverse event by 38% when taken concurrently with warfarin. It has been suggested that ginkgo has to be taken for at least 2-3 weeks to have a significant effect on platelet aggregation. However, a meta-analysis of 18 studies using standardized ginkgo extracts, 80-480 mg daily for up to 32 weeks, did not find a significant effect on platelet aggregation, fibrinogen concentration, or PT/aPTT. In addition, a single dose of ginkgo plus clopidogrel or ticlopidine does not seem to significantly increase bleeding time or platelet aggregation. Also, taking ginkgo leaf extract daily for 8 days in conjunction with rivaroxaban does not affect anti-factor Xa activity; however, this study did not evaluate bleeding time.
Anticonvulsants
Theoretically, ginkgo might reduce the effectiveness of anticonvulsants.
Ginkgo seeds contain ginkgotoxin. Large amounts of ginkgotoxin can cause neurotoxicity and seizure. Ginkgotoxin is present in much larger amounts in ginkgo seeds than leaves. Ginkgo leaf extract contains trace amounts of ginkgotoxin. The amount of ginkgotoxin in ginkgo leaf and leaf extract seems unlikely to cause toxicity. However, there are anecdotal reports of seizure occurring after use of ginkgo leaf both in patients without a history of seizure disorder and in those with previously well-controlled epilepsy.
Antidiabetes Drugs
Theoretically, taking ginkgo with antidiabetes drugs might alter the response to antidiabetes drugs.
Ginkgo leaf extract seems to alter insulin secretion and metabolism, and might affect blood glucose levels in people with type 2 diabetes. The effect of ginkgo seems to differ depending on the insulin and treatment status of the patient. In diet-controlled diabetes patients with hyperinsulinemia, taking ginkgo does not seem to significantly affect insulin or blood glucose levels. In patients with hyperinsulinemia who are treated with oral hypoglycemic agents, taking ginkgo seems to decrease insulin levels and increase blood glucose following an oral glucose tolerance test. Researchers speculate that this could be due to ginkgo-enhanced hepatic metabolism of insulin. In patients with pancreatic exhaustion, taking ginkgo seems to stimulate pancreatic beta-cells, resulting in increased insulin and C-peptide levels, but with no significant change in blood glucose levels in response to an oral glucose tolerance test.
Atorvastatin (Lipitor)
Theoretically, ginkgo might decrease the levels and clinical effects of atorvastatin.
In humans, intake of ginkgo extract appears to increase atorvastatin clearance, reducing the area under the curve of atorvastatin by 10% to 14% and the maximum concentration by 29%. However, this interaction does not appear to affect cholesterol synthesis and absorption. Further, a model in rats with hyperlipidemia suggests that administering ginkgo extract does not impact blood levels of atorvastatin and leads to lower total cholesterol, low-density lipoprotein cholesterol, and triglycerides when compared with rats given atorvastatin alone.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Laboratory research suggests that ginkgo leaf extract can mildly inhibit CYP1A2 enzymes. However, clinical research suggests ginkgo might not affect CYP1A2. Until more is known, use ginkgo cautiously in patients taking drugs metabolized by these enzymes.
Cytochrome P450 2C19 (Cyp2C19) Substrates
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP2C19.
Some clinical research shows that a specific ginkgo leaf extract (Remembrance, Herbs Product LTD) 140 mg twice daily can induce CYP2C19 enzymes and potentially decrease levels of drugs metabolized by these enzymes. However, other clinical research shows that taking ginkgo 120 mg twice daily for 12 days has no effect on levels of drugs metabolized by CYP2C19.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, ginkgo might increase levels of drugs metabolized by CYP2C9.
In vitro, a specific standardized extract of ginkgo leaf (EGb 761) inhibits CYP2C9 activity . The terpenoid (ginkgolides) and flavonoid (quercetin, kaempferol, etc.) constituents seem to be responsible for this effect. Most ginkgo extracts contain some amount of these constituents. Therefore, other ginkgo leaf extracts might also inhibit the CYP2C9 enzyme. However, clinical research suggests that ginkgo might not have a significant effect on CYP2C9 in humans. Ginkgo does not seem to significantly affect the pharmacokinetics of CYP2C9 substrates diclofenac or tolbutamide.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
There is conflicting evidence about whether ginkgo induces or inhibits CYP3A4. Ginkgo does not appear to affect hepatic CYP3A4. However, it is not known if ginkgo affects intestinal CYP3A4. Preliminary clinical research suggests that taking ginkgo does not significantly affect levels of donepezil, lopinavir, or ritonavir, which are all CYP3A4 substrates. Other clinical research also suggests ginkgo does not significantly affect CYP3A4 activity. However, there are two case reports of decreased efavirenz concentrations and increased viral load in patients taking ginkgo. It is suspected that terpenoids from the ginkgo extract reduced drug levels by inducing cytochrome P450 3A4 (CYP3A4).
Efavirenz (Sustiva)
Theoretically, ginkgo might decrease the levels and clinical effects of efavirenz.
There are two case reports of decreased efavirenz concentrations and increased viral load in patients taking ginkgo. In one case, an HIV-positive male experienced over a 50% decrease in efavirenz levels over the course of 14 months while taking ginkgo extract. HIV-1 RNA copies also increased substantially, from less than 50 to more than 1500. It is suspected that terpenoids from the ginkgo extract reduced drug levels by inducing cytochrome P450 3A4 (CYP3A4). In another case report, a patient stable on antiviral therapy including efavirenz for 10 years, had an increase in viral load from <50 copies/mL to 1350 copies/mL after 2 months of taking a combination of supplements including ginkgo. After stopping ginkgo, the viral load was again controlled with the same antiviral therapy regimen.
Ibuprofen (Advil, Others)
Theoretically, ginkgo might increase the risk of bleeding when used with ibuprofen.
Ginkgo might have antiplatelet effects and has been associated with several case reports of spontaneous bleeding. In one case, a 71-year-old male had taken a specific ginkgo extract (Gingium, Biocur) 40 mg twice daily for 2.5 years. About 4 weeks after starting ibuprofen 600 mg daily he experienced a fatal intracerebral hemorrhage. However, the antiplatelet effects of ginkgo have been questioned. A meta-analysis and other studies have not found a significant antiplatelet effect with standardized ginkgo extracts, 80 mg to 480 mg taken daily for up to 32 weeks.
P-Glycoprotein Substrates
Theoretically, taking ginkgo with P-glycoprotein substrates might increase the levels and adverse effects of these substrates.
A small clinical study in healthy volunteers shows that using ginkgo leaf extract 120 mg orally three times daily for 14 days can increase levels of the P-glycoprotein substrate, talinolol, by 36% in healthy male individuals. However, single doses of ginkgo do not have the same effect.
Risperidone (Risperdal)
Theoretically, taking ginkgo with risperidone might increase the levels and adverse effects of risperidone.
A single case of priapism has been reported for a 26-year-old male with schizophrenia who used risperidone 3 mg daily along with ginkgo extract 160 mg daily. Risperidone is metabolized by cytochrome P450 (CYP) 2D6 and CYP3A4. CYP3A4 activity might be affected by ginkgo. Theoretically, ginkgo may inhibit the metabolism of risperidone and increase the risk of adverse effects.
Rosiglitazone (Avandia)
Theoretically, ginkgo might decrease the levels and clinical effects of rosiglitazone.
Animal research shows that ginkgo leaf extract orally 100 or 200 mg/kg daily for 10 days alters the pharmacodynamics of rosiglitazone in a dose-dependent manner. The 100 mg/kg and 200 mg/kg doses reduce the area under the concentration time curve (AUC) of rosiglitazone by 39% and 52%, respectively, and the half-life by 28% and 39%, respectively. It is hypothesized that these changes may be due to induction of cytochrome P450 2C8 by ginkgo.
Seizure Threshold Lowering Drugs
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Ginkgo seeds contain ginkgotoxin. Large amounts of ginkgotoxin can cause neurotoxicity and seizure. Ginkgotoxin is present in much larger amounts in ginkgo seeds than leaves. Ginkgo leaf extract contains trace amounts of ginkgotoxin. The amount of ginkgotoxin in ginkgo leaf and leaf extract seems unlikely to cause toxicity. However, there are anecdotal reports of seizure occurring after use of ginkgo leaf both in patients without a history of seizure disorder and in those with previously well-controlled epilepsy.
Simvastatin (Zocor)
Theoretically, ginkgo might decrease the levels and clinical effects of simvastatin.
Clinical research shows that taking ginkgo extract can reduce the area under the curve and maximum concentration of simvastatin by 32% to 39%. However, ginkgo extract does not seem to affect the cholesterol-lowering ability of simvastatin.
Sofosbuvir (Sovaldi)
Theoretically, ginkgo might increase the levels and clinical effects of sofosbuvir.
Animal research in rats shows that giving a ginkgo extract 25 mg/kg orally daily for 14 days increases the area under the concentration time curve (AUC) after a single sofosbuvir dose of 40 mg/kg by 11%, increases the half-life by 60%, and increases the plasma concentration at 4 hours by 38%. This interaction appears to be related to the inhibition of intestinal P-glycoprotein by ginkgo.
Tacrolimus (Prograf)
Theoretically, ginkgo might increase the blood levels of tacrolimus.
In vitro evidence suggests that certain biflavonoids in ginkgo leaves (i.e. amentoflavone, ginkgetin, bilobetin) may inhibit the metabolism of tacrolimus by up to 50%. This interaction appears to be time-dependent and due to inhibition of cytochrome P450 (CYP) 3A4 by these bioflavonoids. In rats given tacrolimus 1 mg/kg orally, amentoflavone was shown to increase the area under the concentration time curve (AUC) of tacrolimus by 3.8-fold.
Trazodone (Desyrel)
Theoretically, ginkgo might increase the levels and clinical effects of trazodone.
In a case report, an Alzheimer patient taking trazodone 20 mg twice daily and ginkgo leaf extract 80 mg twice daily for four doses became comatose. The coma was reversed by administration of flumazenil (Romazicon). Coma might have been induced by excessive GABA-ergic activity. Ginkgo flavonoids are thought to have GABA-ergic activity and act directly on benzodiazepine receptors. Ginkgo might also increase metabolism of trazodone to active GABA-ergic metabolites, possibly by inducing cytochrome P450 3A4 (CYP3A4) metabolism.
Warfarin (Coumadin)
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin.
Several pharmacodynamic studies suggest that ginkgo inhibits platelet aggregation. It is thought that the ginkgo constituent, ginkgolide B, displaces platelet-activating factor (PAF) from its binding sites, decreasing blood coagulation. Several case reports have documented serious bleeding events in patients taking ginkgo. Information from a medical database suggests that when taken concurrently with warfarin, ginkgo increases the risk of a bleeding adverse event by 38%. There is also some evidence that ginkgo leaf extract can inhibit cytochrome P450 2C9, an enzyme that metabolizes warfarin. This could result in increased warfarin levels. However, population and clinical research has produced mixed results. Clinical research in healthy people suggests that ginkgo has no effect on INR, or the pharmacokinetics or pharmacodynamics of warfarin. A meta-analysis of 18 studies using standardized ginkgo extracts, 80 mg to 480 mg daily for up to 32 weeks, did not find a significant effect on platelet aggregation, fibrinogen concentration, or PT/aPTT. There is also some preliminary clinical research that suggests ginkgo might not significantly increase the effects of warfarin in patients that have a stable INR.
Nifedipine (Procardia)
Theoretically, taking ginkgo with oral, but not intravenous, nifedipine might increase levels and adverse effects of nifedipine.
Animal research and some clinical evidence suggests that taking ginkgo leaf extract orally in combination with oral nifedipine might increase nifedipine levels and cause increased side effects, such as headaches, dizziness, and hot flushes. However, taking ginkgo orally does not seem to affect the pharmacokinetics of intravenous nifedipine.
Omeprazole (Prilosec)
Theoretically, taking ginkgo with omeprazole might decrease the levels and clinical effects of omeprazole.
Clinical research shows that a specific ginkgo leaf extract (Remembrance, Herbs Product LTD) 140 mg twice daily can induce cytochrome P450 (CYP) 2C19 enzymes and decrease levels of omeprazole by about 27% to 42%.
Quercetin
Antidiabetes Drugs
Theoretically, concomitant use of quercetin and antidiabetes drugs might increase the risk of hypoglycemia.
Clinical research suggests that a combination of quercetin, myricetin, and chlorogenic acid reduce levels of fasting glucose in patients with type 2 diabetes, including those already taking antidiabetes agents. The effect of quercetin alone is unknown.
Antihypertensive Drugs
Theoretically, taking quercetin with antihypertensive drugs might increase the risk of hypotension.
Quercetin can modestly decrease blood pressure in people with mild hypertension. Theoretically, it might have additive blood pressure lowering effects when used with antihypertensive drugs.
Cyclosporine (Neoral, Sandimmune)
Theoretically, concomitant use might increase the levels and adverse effects of cyclosporine.
A small study in healthy volunteers shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of a single dose of cyclosporine, possibly due to inhibition of p-glycoprotein or cytochrome P450 3A4 (CYP3A4), which metabolizes cyclosporin.
Cytochrome P450 2C8 (Cyp2C8) Substrates
Theoretically, concomitant use might increase the levels and adverse effects of CYP2C8 substrates.
In vitro research shows that quercetin inhibits CYP2C8. Inhibition of paclitaxel (Taxol) metabolism via CYP2C8 has been reported in vitro. However, a small study in humans found no effect of quercetin on rosiglitazone (Avandia), which is also a CYP2C8 substrate.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, concomitant use might increase the levels and adverse effects of CYP2C9 substrates.
A small clinical study in healthy volunteers shows that taking quercetin 500 mg twice daily for 10 days prior to taking diclofenac, a CYP2C9 substrate, increases diclofenac plasma levels by 75% and prolongs the half-life by 32.5%. Animal research also shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of losartan (Cozaar), a substrate of CYP2C9. Furthermore, laboratory research shows that quercetin inhibits CYP2C9.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
In vitro research show that quercetin inhibits CYP2D6. This effect has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
A small clinical study in healthy volunteers shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of a single dose of cyclosporine (Neoral, Sandimmune), a substrate of CYP3A4. Animal research also shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of losartan (Cozaar) and quetiapine (Seroquel), substrates of CYP3A4. Other laboratory research also shows that quercetin inhibits CYP3A4. However, one clinical study shows that quercetin can increase the metabolism of midazolam, a substrate of CYP3A4, and decrease serum concentrations of midazolam by about 24% in some healthy individuals, suggesting possible induction of CYP3A4.
Diclofenac (Voltaren, Others)
Theoretically, concomitant use might increase the levels and adverse effects of diclofenac.
A small clinical study in healthy volunteers shows that taking quercetin 500 mg twice daily for 10 days prior to taking diclofenac increases diclofenac plasma levels by 75% and prolongs the half-life by 32.5%. This is thought to be due to inhibition of CYP2C9 by quercetin.
Losartan (Cozaar)
Theoretically, concomitant use might increase the effects and adverse effects of losartan and decrease the effects of its active metabolite.
Animal research shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of losartan (Cozaar) while decreasing plasma levels of losartan's active metabolite. This metabolite, which is around 10-fold more potent than losartan, is the result of cytochrome P450 (CYP) 2C9- and CYP3A4-mediated transformation of losartan. Additionally, in vitro research shows that quercetin may inhibit P-glycoprotein-mediated efflux of losartan from the intestines, resulting in increased absorption of losartan. These results suggest that concomitant use of quercetin and losartan might increase systemic exposure to losartan while also decreasing plasma concentrations of losartan's active and more potent metabolite.
Midazolam (Versed)
Theoretically, concomitant use might decrease the levels and effects of midazolam.
A small clinical study in healthy volunteers shows that quercetin can increase the metabolism of midazolam, with a decrease in AUC of about 24%.
Mitoxantrone
Theoretically, quercetin might increase the effects and adverse effects of mitoxantrone.
In vitro research shows that quercetin increases the intracellular accumulation and cytotoxicity of mitoxantrone, possibly through inhibition of breast cancer resistance protein (BCRP), of which mitoxantrone is a substrate. So far, this interaction has not been reported in humans.
Organic Anion Transporter 1 (Oat1) Substrates
Theoretically, concomitant use might increase the effects and adverse effects of OAT1 substrates.
In vitro research shows that quercetin is a strong non-competitive inhibitor of OAT1, with half-maximal inhibitory concentration (IC50) values less than 10 mcM. So far, this interaction has not been reported in humans.
Organic Anion Transporter 3 (Oat3) Substrates
Theoretically, concomitant use might increase the effects and adverse effects of OAT3 substrates.
In vitro research shows that quercetin is a strong non-competitive inhibitor of OAT3, with half-maximal inhibitory concentration (IC50) values as low as 0.75 mcM. So far, this interaction has not been reported in humans.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Theoretically, concomitant use might increase the effects and adverse effects of OATP substrates.
In vitro evidence shows that quercetin can inhibit organic anion-transporting peptide (OATP) 1B1-mediated uptake of estrone-3-sulfate and pravastatin. Furthermore, clinical research in healthy males shows that intake of quercetin along with pravastatin increases the AUC of pravastatin by 24%, prolongs its half-life by 14%, and decreases its apparent clearance by 18%, suggesting that quercetin modestly inhibits the uptake of pravastatin in hepatic cells.
P-Glycoprotein Substrates
Theoretically, concomitant use might alter the effects and adverse effects of P-glycoprotein substrates.
There is preliminary evidence that quercetin inhibits the gastrointestinal P-glycoprotein efflux pump, which might increase the bioavailability and serum levels of drugs transported by the pump. A small study in healthy volunteers reported that pretreatment with quercetin increased bioavailability and plasma levels after a single dose of cyclosporine (Neoral, Sandimmune). Also, two small studies have shown that quercetin might decrease the absorption of talinolol, a substrate transported by the gastrointestinal P-glycoprotein efflux pump. However, in another small study, several days of quercetin treatment did not significantly affect the pharmacokinetics of saquinavir (Invirase). The reason for these discrepancies is not entirely clear. Until more is known, use quercetin cautiously in combination with P-glycoprotein substrates.
Pravastatin (Pravachol)
Theoretically, concomitant use might increase the effects and adverse effects of pravastatin.
In vitro evidence shows that quercetin can inhibit OATP 1B1-mediated uptake of pravastatin. Also, preliminary clinical research in healthy males shows that intake of quercetin along with pravastatin increases the maximum concentration of pravastatin by 24%, prolongs its half-life by 14%, and decreases its apparent clearance by 18%, suggesting that quercetin modestly inhibits the uptake of pravastatin in hepatic cells.
Prazosin (Minipress)
Theoretically, quercetin might increase the effects and adverse effects of prazosin.
In vitro research shows that quercetin inhibits the transcellular efflux of prazosin, possibly through inhibition of breast cancer resistance protein (BCRP), of which prazosin is a substrate. BCRP is an ATP-binding cassette efflux transporter in the intestines, kidneys, and liver. So far, this interaction has not been reported in humans.
Quetiapine (Seroquel)
Theoretically, concomitant use might increase the effects and adverse effects of quetiapine.
Animal research shows that pretreatment with quercetin can increase plasma levels of quetiapine and prolong its clearance, possibly due to inhibition of cytochrome P450 3A4 (CYP3A4) by quercetin. Additionally, the brain-to-plasma ratio of quetiapine concentrations increased, possibly due to inhibition of P-glycoprotein at the blood-brain barrier. This interaction has not been reported in humans.
Quinolone Antibiotics
Theoretically, concomitant use might inhibit the effects of quinolone antibiotics.
In vitro, quercetin binds to the DNA gyrase site on bacteria, which may interfere with the activity of quinolone antibiotics.
Sulfasalazine (Azulfidine)
Theoretically, quercetin might increase the effects and adverse effects of sulfasalazine.
Animal research shows that quercetin increases the maximum serum concentration (Cmax) and area under the curve (AUC) of sulfasalazine, possibly through inhibition of breast cancer resistance protein (BCRP), of which sulfasalazine is a substrate. So far, this interaction has not been reported in humans.
Warfarin (Coumadin)
Theoretically, quercetin may increase the risk of bleeding if used with warfarin.
Animal and in vitro studies show that quercetin might increase serum levels of warfarin. Quercetin and warfarin have the same human serum albumin (HSA) binding site, and in vitro research shows that quercetin has stronger affinity for the HSA binding site and can theoretically displace warfarin, causing higher serum levels of warfarin. Animal research shows that taking quercetin for 2 weeks before initiating warfarin increases the maximum serum level of warfarin by 30%, the half-life by 10%, and the overall exposure by 63% when compared with control. Concomitant administration of quercetin and warfarin, without quercetin pre-treatment, also increased these measures, but to a lesser degree. Researchers theorize that inhibition of CYP3A4 by quercetin may explain these effects. So far, this interaction has not been reported in humans.
Vitamin B3
Alcohol (Ethanol)
Concomitant use of alcohol and niacin might increase the risk of flushing and hepatotoxicity.
Alcohol can exacerbate the flushing and pruritus associated with niacin. Large doses of niacin might also exacerbate liver dysfunction associated with chronic alcohol use. A case report describes delirium and lactic acidosis in a patient taking niacin 3 grams daily who ingested 1 liter of wine. Advise patients to avoid large amounts of alcohol while taking niacin.
Allopurinol (Zyloprim)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as allopurinol.
Large doses of niacin can reduce urinary excretion of uric acid, potentially resulting in hyperuricemia. Doses of uricosurics such as allopurinol might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Anticoagulant/Antiplatelet Drugs
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Several cases of clotting factor synthesis deficiency and coagulopathy have been reported in patients taking sustained-release niacin. Also, thrombocytopenia has been reported in patients treated with niacin or niacin plus lovastatin.
Antidiabetes Drugs
Niacin can increase blood glucose levels and may diminish the effects of antidiabetes drugs.
Niacin impairs glucose tolerance in a dose-dependent manner, probably by causing or aggravating insulin resistance and increasing hepatic production of glucose. In diabetes patients, niacin 4.5 grams daily for 5 weeks can increase plasma glucose by an average of 16% and glycated hemoglobin (HbA1c) by 21%. However, lower doses of 1.5 grams daily or less appear to have minimal effects on blood glucose. In some patients, glucose levels increase when niacin is started, but then return to baseline when a stable dose is reached. Up to 35% of patients with diabetes may need adjustments in hypoglycemic therapy when niacin is added.
Antihypertensive Drugs
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
The vasodilating effects of niacin can cause hypotension. Furthermore, some clinical evidence suggests that a one-hour infusion of niacin can reduce systolic, diastolic, and mean blood pressure in hypertensive patients. This effect is not observed in normotensive patients.
Bile Acid Sequestrants
Bile acid sequestrants can bind niacin and decrease absorption. Separate administration by 4-6 hours to avoid an interaction.
In vitro studies show that colestipol (Colestid) binds about 98% of available niacin and cholestyramine (Questran) binds 10% to 30%.
Gemfibrozil (Lopid)
Theoretically, concomitant use of niacin and gemfibrozil might increase the risk of myopathy in some patients.
A case of myopathy from concomitant use of niacin and gemfibrozil has been reported. Niacin alone has also been associated with cases of myopathy. Using gemfibrozil with niacin might further increase the risk of developing myopathy.
Hepatotoxic Drugs
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Niacin has been associated with cases of liver toxicity, especially when used in pharmacologic doses. Sustained-release niacin preparations appear to be associated with a higher risk of hepatotoxicity than immediate-release niacin.
Hmg-Coa Reductase Inhibitors ("Statins")
Theoretically, concomitant use of niacin and statins might increase the risk of myopathy and rhabdomyolysis in some patients.
Some case reports have raised concerns that niacin might increase the risk of myopathy and rhabdomyolysis when combined with statins. However, a significantly increased risk of myopathy has not been demonstrated in clinical trials, including those using an FDA-approved combination of lovastatin and niacin (Advicor).
Probenecid (Benemid)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as probenecid.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as probenecid might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Sulfinpyrazone (Anturane)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as sulfinpyrazone.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as sulfinpyrazone might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Thyroid Hormone
Theoretically, niacin might antagonize the therapeutic effects of thyroid hormones.
Clinical research and case reports suggests that taking niacin can reduce serum levels of thyroxine-binding globulin by up to 25% and moderately reduce levels of thyroxine (T4). Patients taking thyroid hormone for hypothyroidism might need dose adjustments when using niacin.
Transdermal Nicotine (Nicoderm)
Theoretically, concomitant use of niacin and transdermal nicotine might increase the risk of flushing and dizziness.
Niacin and nicotine can both cause flushing and dizziness.
Warfarin (Coumadin)
There is limited evidence that niacin may increase the anticoagulant effects of warfarin.
In a case report, a patient on warfarin developed an elevated international normalized ratio (INR) of 3.9 after taking niacin for two weeks. The patient's INR was previously stable, ranging between 2 and 3 in recent months, and no other medication changes were identified. The elevated INR returned to therapeutic range within 4 days following the discontinuation of niacin.
Aspirin
Large doses of aspirin might alter the clearance of niacin.
Aspirin is often used with niacin to reduce niacin-induced flushing. Doses of 80-975 mg aspirin have been used, but 325 mg appears to be optimal. Aspirin also seems to reduce the clearance of niacin by competing for glycine conjugation. Taking aspirin 1 gram seems to reduce niacin clearance by 45%. This is probably a dose-related effect and not clinically significant with the more common aspirin dose of 325 mg.
Vitamin D3
Aluminum
Vitamin D might increase aluminum absorption and toxicity, but this has only been reported in people with renal failure.
The protein that transports calcium across the intestinal wall can also bind and transport aluminum. This protein is stimulated by vitamin D, which may therefore increase aluminum absorption. This mechanism may contribute to increased aluminum levels and toxicity in people with renal failure, when they take vitamin D and aluminum-containing phosphate binders chronically.
Atorvastatin (Lipitor)
Vitamin D might reduce absorption of atorvastatin.
A small, low-quality clinical study shows that taking vitamin D reduces levels of atorvastatin and its active metabolites by up to 55%. However, while atorvastatin levels decreased, total cholesterol, low-density lipoprotein (LDL) cholesterol, and high-density lipoprotein (HDL) cholesterol levels did not substantially change. Atorvastatin is metabolized in the gut by CYP3A4 enzymes, and researchers theorized that vitamin D might induce CYP3A4, causing reduced levels of atorvastatin. However, this proposed mechanism was not specifically studied.
Calcipotriene (Dovonex)
Taking calcipotriene with vitamin D increases the risk for hypercalcemia.
Calcipotriene is a vitamin D analog used topically for psoriasis. It can be absorbed in sufficient amounts to cause systemic effects, including hypercalcemia. Theoretically, combining calcipotriene with vitamin D supplements might increase the risk of hypercalcemia.
Digoxin (Lanoxin)
Theoretically, hypercalcemia induced by high-dose vitamin D can increase the risk of arrhythmia from digoxin.
High doses of vitamin D can cause hypercalcemia. Hypercalcemia increases the risk of fatal cardiac arrhythmias with digoxin. Avoid vitamin D doses above the tolerable upper intake level (4000 IU daily for adults) and monitor serum calcium levels in people taking vitamin D and digoxin concurrently.
Diltiazem (Cardizem, Others)
Theoretically, hypercalcemia induced by high-dose vitamin D can reduce the therapeutic effects of diltiazem for arrhythmia.
High doses of vitamin D can cause hypercalcemia. Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically this could also occur with diltiazem. Avoid vitamin D doses above the tolerable upper intake level (4000 IU daily for adults) and monitor serum calcium levels in people taking vitamin D and diltiazem concurrently.
Thiazide Diuretics
Theoretically, taking thiazide diuretics and high-dose vitamin D can increase the risk of hypercalcemia.
Thiazide diuretics decrease urinary calcium excretion, which could lead to hypercalcemia if vitamin D supplements are taken concurrently. This has been reported in people being treated with vitamin D for hypoparathyroidism, and also in elderly people with normal parathyroid function who were taking a thiazide, vitamin D, and calcium-containing antacids daily.
Verapamil (Calan, Others)
Hypercalcemia induced by high-dose vitamin D can reduce the therapeutic effects of verapamil for arrhythmia.
Hypercalcemia due to high doses of vitamin D can reduce the effectiveness of verapamil in atrial fibrillation. Avoid vitamin D doses above the tolerable upper intake level (4000 IU daily for adults) and monitor serum calcium levels in people taking vitamin D and verapamil concurrently.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
There is some concern that vitamin D might induce CYP3A4. In vitro research suggests that vitamin D induces CYP3A4 transcription. Additionally, observational research has found that increased UV light exposure and serum vitamin D levels are associated with decreased serum levels of CYP3A4 substrates such as tacrolimus and sirolimus, while no association between UV light exposure or vitamin D levels and levels of mycophenolic acid, a non-CYP3A4 substrate, was found. A small, low-quality clinical study shows that taking vitamin D reduces levels of the CYP3A4 substrate atorvastatin and its active metabolites by up to 55%; however, the clinical effects of atorvastatin were not reduced. While researchers theorized that vitamin D might induce CYP3A4, this proposed mechanism was not specifically studied.
Vitamin A
Retinoids
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Retinoids, which are vitamin A derivatives, could have additive toxic effects when taken with vitamin A supplements.
Hepatotoxic Drugs
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
The tolerable upper intake level (UL) is the highest level of intake that is likely to pose no risk of adverse effects. Doses of vitamin A above the UL can cause hepatotoxicity, ranging from elevated liver enzymes to liver failure.
Tetracycline Antibiotics
Theoretically, taking tetracycline antibiotics with high doses of vitamin A can increase the risk of pseudotumor cerebri.
Benign intracranial hypertension (pseudotumor cerebri) can occur with tetracyclines and with acute or chronic vitamin A toxicity. Case reports suggest that taking tetracyclines and vitamin A concurrently can increase the risk of this condition. Avoid high doses of vitamin A in people taking tetracyclines chronically.
Warfarin (Coumadin)
Theoretically, high doses of vitamin A could increase the risk of bleeding with warfarin.
Vitamin A toxicity is associated with hemorrhage and hypoprothrombinemia, possibly due to vitamin K antagonism. Advise patients taking warfarin to avoid doses of vitamin A above the tolerable upper intake level of 10,000 IU/day for adults.
Magnesium
Levodopa/Carbidopa (Sinemet)
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Clinical research in healthy volunteers shows that taking magnesium oxide 1000 mg with levodopa 100 mg/carbidopa 10 mg reduces the area under the curve (AUC) of levodopa by 35% and of carbidopa by 81%. In vitro and animal research shows that magnesium produces an alkaline environment in the digestive tract, which might lead to degradation and reduced bioavailability of levodopa/carbidopa.
Aminoglycoside Antibiotics
Concomitant use of aminoglycoside antibiotics and magnesium can increase the risk for neuromuscular weakness.
Both aminoglycosides and magnesium reduce presynaptic acetylcholine release, which can lead to neuromuscular blockade and possible paralysis. This is most likely to occur with high doses of magnesium given intravenously.
Antacids
Use of acid reducers may reduce the laxative effect of magnesium oxide.
A retrospective analysis shows that, in the presence of H2 receptor antagonists (H2RAs) or proton pump inhibitors (PPIs), a higher dose of magnesium oxide is needed for a laxative effect. This may also occur with antacids. Under acidic conditions, magnesium oxide is converted to magnesium chloride and then to magnesium bicarbonate, which has an osmotic laxative effect. By reducing acidity, antacids may reduce the conversion of magnesium oxide to the active bicarbonate salt.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after magnesium containing products.
Bisphosphonates
Magnesium can decrease absorption of bisphosphonates.
Cations, including magnesium, can decrease bisphosphonate absorption. Advise patients to separate doses of magnesium and these drugs by at least 2 hours.
Calcium Channel Blockers
Magnesium can have additive effects with calcium channel blockers, although evidence is conflicting.
Magnesium inhibits calcium entry into smooth muscle cells and may therefore have additive effects with calcium channel blockers. Severe hypotension and neuromuscular blockades may occur when nifedipine is used with intravenous magnesium, although some contradictory evidence suggests that concurrent use of magnesium with nifedipine does not increase the risk of neuromuscular weakness. High doses of magnesium could theoretically have additive effects with other calcium channel blockers.
Digoxin
Magnesium salts may reduce absorption of digoxin.
Clinical evidence suggests that treatment with oral magnesium hydroxide or magnesium trisilicate reduces absorption of digoxin from the intestines. This may reduce the blood levels of digoxin and decrease its therapeutic effects.
Potassium-Sparing Diuretics
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Potassium-sparing diuretics also have magnesium-sparing properties, which can counteract the magnesium losses associated with loop and thiazide diuretics. Theoretically, increased magnesium levels could result from concomitant use of potassium-sparing diuretics and magnesium supplements.
Quinolone Antibiotics
Magnesium decreases absorption of quinolones.
Magnesium can form insoluble complexes with quinolones and decrease their absorption. Advise patients to take these drugs at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Skeletal Muscle Relaxants
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Parenteral magnesium shortens the time to onset of skeletal muscle relaxants by about 1 minute and prolongs the duration of action by about 2 minutes. Magnesium potentiates the effects of skeletal muscle relaxants by decreasing calcium-mediated release of acetylcholine from presynaptic nerve terminals, reducing postsynaptic sensitivity to acetylcholine, and having a direct effect on the membrane potential of myocytes. Magnesium also has vasodilatory actions and increases cardiac output, allowing a greater amount of muscle relaxant to reach the motor end plate. A clinical study found that low-dose rocuronium (0.45 mg/kg), when given after administration of magnesium 30 mg/kg over 10 minutes, has an accelerated onset of effect, which matches the onset of effect seen with a full-dose rocuronium regimen (0.6 mg/kg). In another clinical study, onset times for rocuronium doses of 0.3, 0.6, and 1.2 mg/kg were 86, 76, and 50 seconds, respectively, when given alone, but were reduced to 66, 44, and 38 seconds, respectively, when the doses were given after a 15-minute infusion of magnesium sulfate 60 mg/kg. Giving intraoperative intravenous magnesium sulfate, 50 mg/kg loading dose followed by 15 mg/kg/hour, reduces the onset time of rocuronium, enhances its clinical effects, reduces the dose of intraoperative opiates, and prolongs the spontaneous recovery time. It does not affect the activity of subsequently administered neostigmine.
Sulfonylureas
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Clinical research shows that administration of magnesium hydroxide with glyburide increases glyburide absorption, increases maximal insulin response by 35-fold, and increases the risk of hypoglycemia, when compared with glyburide alone. A similar interaction occurs between magnesium hydroxide and glipizide. The mechanism of this effect appears to be related to the elevation of gastrointestinal pH by magnesium-based antacids, increasing solubility and enhancing absorption of sulfonylureas.
Tetracycline Antibiotics
Magnesium decreases absorption of tetracyclines.
Magnesium can form insoluble complexes with tetracyclines in the gut and decrease their absorption and antibacterial activity. Advise patients to take these drugs 1 hour before or 2 hours after magnesium supplements.
Anticoagulant/Antiplatelet Drugs
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
In vitro evidence shows that magnesium sulfate inhibits platelet aggregation, even at low concentrations. Some preliminary clinical evidence shows that infusion of magnesium sulfate increases bleeding time by 48% and reduces platelet activity. However, other clinical research shows that magnesium does not affect platelet aggregation, although inhibition of platelet-dependent thrombosis can occur.
Gabapentin (Neurontin)
Gabapentin absorption can be decreased by magnesium.
Clinical research shows that giving magnesium oxide orally along with gabapentin decreases the maximum plasma concentration of gabapentin by 33%, time to maximum concentration by 36%, and area under the curve by 43%. Advise patients to take gabapentin at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Sevelamer (Renagel, Renvela)
Sevelamer may increase serum magnesium levels.
In patients on hemodialysis, sevelamer use was associated with a 0.28 mg/dL increase in serum magnesium. The mechanism of this interaction remains unclear.
Zinc
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Theoretically, zinc might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after zinc containing products.
Cephalexin (Keflex)
Zinc might decrease cephalexin levels by chelating with cephalexin in the gut and preventing its absorption.
A pharmacokinetic study shows that zinc sulfate 250 mg taken concomitantly with cephalexin 500 mg decreases peak levels of cephalexin by 31% and reduces the exposure to cephalexin by 27%. Also, taking zinc sulfate 3 hours before cephalexin decreases peak levels of cephalexin by 11% and reduces the exposure to cephalexin by 18%. By decreasing cephalexin levels, zinc might increase the risk of treatment failure. This effect does not occur when zinc is taken 3 hours after the cephalexin dose. To avoid an interaction, advise patients take zinc sulfate 3 hours after taking cephalexin.
Cisplatin (Platinol-Aq)
Theoretically, zinc might interfere with the therapeutic effects of cisplatin.
Animal research suggests that zinc stimulates tumor cell production of the protein metallothionein, which binds and inactivates cisplatin. It is not known whether zinc supplements or high dietary zinc intake can cause clinically significant interference with cisplatin therapy. Cisplatin might also increase zinc excretion.
Integrase Inhibitors
Theoretically, taking zinc along with integrase inhibitors might decrease the levels and clinical effects of these drugs.
Zinc is a divalent cation. Pharmacokinetic studies have shown that other divalent cations such as calcium and iron can decrease blood levels of the integrase inhibitor dolutegravir through chelation.
Penicillamine (Cuprimine, Depen)
Zinc might reduce the levels and clinical effects of penicillamine.
By forming an insoluble complex with penicillamine, zinc interferes with penicillamine absorption and activity. Zinc supplements reduce the efficacy of low-dose penicillamine (0.5-1 gram/day), but do not seem to affect higher doses (1-2.75 gram/day), provided dosing times are separated. Advise patients to take zinc and penicillamine at least 2 hours apart.
Quinolone Antibiotics
Zinc can decrease the levels and clinical effects of quinolones antibiotics.
Quinolones form complexes with zinc in the gastrointestinal tract, reducing absorption of both the quinolone and zinc if taken at the same time. Advise patients to take these drugs at least 2 hours before, or 4-6 hours after, zinc supplements.
Ritonavir (Norvir)
Zinc modestly reduces levels of ritonavir.
Clinical research shows that zinc might reduce serum ritonavir levels by chelating with ritonavir in the gut and preventing its absorption. In patients with HIV, ritonavir is taken with atazanavir to prevent the metabolism and increase the effects of atazanavir. A pharmacokinetic study shows that, in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate (Solvazinc tablets) 125 mg as a single dose or as multiple daily doses for 2 weeks reduces plasma levels of ritonavir by about 16%. However, atazanavir levels still remains high enough to prevent HIV virus replication. Therefore, the decrease in ritonavir levels is not likely to be clinically significant.
Tetracycline Antibiotics
Zinc might reduce levels of tetracycline antibiotics.
Tetracyclines form complexes with zinc in the gastrointestinal tract, which can reduce absorption of both the tetracycline and zinc when taken at the same time. Taking zinc sulfate 200 mg with tetracycline reduces absorption of the antibiotic by 30% to 40%. Demeclocycline and minocycline cause a similar interaction. However, doxycycline does not seem to interact significantly with zinc. Advise patients to take tetracyclines at least 2 hours before, or 4-6 hours after, zinc supplements to avoid any interactions.
Amiloride (Midamor)
Amiloride can modestly reduce zinc excretion and increase zinc levels.
Clinical research shows that amiloride can reduce urinary zinc excretion, especially at doses of 10 mg per day or more. This zinc-sparing effect can help to counteract zinc losses caused by thiazide diuretics, but it is unlikely to cause zinc toxicity at usual amiloride doses. The other potassium-sparing diuretics, spironolactone (Aldactone) and triamterene (Dyrenium), do not seem to have a zinc-sparing effect.
Atazanavir (Reyataz)
Zinc modestly reduces levels of atazanavir, although this effect does not seem to be clinically significant.
Clinical research shows that zinc might decrease serum atazanavir levels by chelating with atazanavir in the gut and preventing its absorption. Although a single dose of zinc sulfate (Solvazinc tablets) 125 mg orally does not affect atazanavir concentrations in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate 125 mg daily for 2 weeks reduces plasma levels of atazanavir by about 22% in these patients. However, despite this decrease, atazanavir levels still remain at high enough concentrations for the prevention of HIV virus replication.
Brand information
Manufacturer and brand details for Optihear, from the product label.
SuperSmart
See all SuperSmart products- Name
- SN Worldwide Unipessoal, Lda
- Street Address
- Avenida Do Infante 66, Edificio Quinta Avenida 1 C
- City
- Funchal
- ZipCode
- 9000-015
Optihear by SuperSmart: Common Questions
Does Optihear by SuperSmart interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take Optihear if I'm pregnant?
Will Optihear help my hearing loss?
What are the most common side effects?
Can I take Optihear with my other supplements?
Is Optihear safe if I have kidney or liver problems?
What's the role of each ingredient in hearing health?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Optihear is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Optihear’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin D
Interacts with 715 drugsVitamin D is a fat-soluble vitamin that helps your body absorb calcium and is important for healthy bones, muscles, and immune function. Many people, especially those with low sun exposure,...
Read the full Vitamin D monograph → Herb & supplement monographZinc
Interacts with 67 drugsZinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but supplements can help correct or prevent a defici...
Read the full Zinc monograph → Herb & supplement monographNiacin
Interacts with 727 drugsNiacin (vitamin B3) is an essential nutrient your body needs for energy and metabolism, and deficiency is uncommon in most developed countries. Prescription-strength niacin has been used to...
Read the full Niacin monograph → Herb & supplement monographGinkgo
Interacts with 1,266 drugsGinkgo is one of the world's most popular herbal supplements, mostly taken to support memory and circulation. The evidence for these uses is mixed and generally weak, and it is not proven to...
Read the full Ginkgo monograph → Herb & supplement monographMagnesium
Interacts with 295 drugsMagnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preventing or correcting deficiency. Some othe...
Read the full Magnesium monograph → Herb & supplement monographQuercetin
Interacts with 1,169 drugsQuercetin is a plant flavonoid with antioxidant and anti-inflammatory properties found in many common foods and sold as a supplement. While early research is interesting for allergies, blood...
Read the full Quercetin monograph → Herb & supplement monographVitamin A
Interacts with 387 drugsVitamin A is an essential nutrient important for vision, skin, immune function, and growth. Most people get enough from a balanced diet, and supplements are mainly useful for correcting a tr...
Read the full Vitamin A monograph →Sources & How We Checked
Optihear's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 416 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Vitamin D 26 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Tatro DS, ed. Drug Interactions Facts. Facts and Comparisons Inc., St. Louis, MO. 1999.
- Koutkia P, Chen TC, Holick MF. Vitamin D intoxication associated with an over-the-counter supplement. N Engl J Med 2001;345:66-7. PubMed
- Bar-Or D, Yoel G. Calcium and calciferol antagonize effect of verapamil in atrial fibrillation. Br Med J 1981;282:1585-6.
- Demontis R, Leflon A, Fournier A, et al. 1 alpha(OH) vitamin D3 increases plasma aluminum in hemodialyzed patients taking AI(OH)3. Clin Nephrol 1986;26:146-9.
- Crowe M, Wollner L, Griffiths RA. Hypercalcemia following vitamin D and thiazide therapy in the elderly. Practitioner 1984;228:312-3.
- Parfitt AM. Thiazide-induced hypercalcemia in vitamin D-treated hypoparathyroidism. Ann Intern Med 1972;77:557-63. PubMed
- Thiazide diuretics and the risk of osteoporosis. Pharmacist's Letter/Prescriber's Letter 2003;19(11):191105.
- Moon J. The role of vitamin D in toxic metal absorption. J Am Coll Nutr 1994;13:559-64.
- Demontis R, Reissi D, Noel C, et al. Indirect clinical evidence that 1alphaOH vitamin D<SUB>3</SUB> increases the intestinal absorption of aluminum. Clin Nephrol 1989;31:123-7.
- Adler AJ, Berlyne GM. Duodenal aluminum absorption in the rat: effect of vitamin D. Am J Physiol 1985;249:G209-13. PubMed
- Schwartz JB. Effects of vitamin D supplementation in atorvastatin-treated patients: A new drug interaction with an unexpected consequence. Clin Pharmacol Ther 2009;85:198-203. PubMed
- Dietary reference intakes for calcium and vitamin D. Institute of Medicine, November 30, 2010. Available at: http://www.iom.edu/~/media/Files/Report%20Files/2010/Dietary-Reference-Intakes-for-Calcium-and-Vitamin-D/Vitamin%20D%20and%20Calcium%202010%20Repo
- Cox KA, Dunn MA. Aluminum toxicity alters the regulation of calbindin-D28k protein and mRNA expression in chick intestine. J Nutr 2001;131:2007-13. PubMed
- Escribano, J., Balaguer, A., Pagone, F., Feliu, A., and Roque, I. Figuls. Pharmacological interventions for preventing complications in idiopathic hypercalciuria. Cochrane.Database.Syst.Rev. 2009;(1):CD004754. PubMed
- Carlton, S., Clopton, D., and Cappuzzo, K. A. Vitamin D deficiency: appropriate replenishment therapies and the effects of vitamin D toxicity. Consult Pharm 2010;25(3):171-177. PubMed
- Wang, H., Xia, N., Yang, Y., and Peng, D. Q. Influence of vitamin D supplementation on plasma lipid profiles: a meta-analysis of randomized controlled trials. Lipids Health Dis. 2012;11:42. PubMed
- Turner AN, Carr Reese P, Fields KS, Anderson J, Ervin M, Davis JA, Fichorova RN, Roberts MW, Klebanoff MA, Jackson RD. A blinded, randomized controlled trial of high-dose vitamin D supplementation to reduce recurrence of bacterial vaginosis. Am J Obstet G PubMed
- Weiner M, Epstein FH. Signs and symptoms of electrolyte disorders. Yale J Biol Med. 1970;43(2):76-109.
- Lappe J, Watson P, Travers-Gustafson D, Recker R, Garland C, Gorham E, Baggerly K, McDonnell SL. Effect of Vitamin D and Calcium Supplementation on Cancer Incidence in Older Women: A Randomized Clinical Trial. JAMA. 2017 Mar 28;317(12):1234-1243. PubMed
- Roth DE, Leung M, Mesfin E, Qamar H, Watterworth J, Papp E. Vitamin D supplementation during pregnancy: state of the evidence from a systematic review of randomised trials. BMJ. 2017;359:j5237. PubMed
- Murai IH, Fernandes AL, Sales LP, et al. Effect of a single high dose of vitamin D3 on hospital length of stay in patients with moderate to severe COVID-19: A randomized clinical trial. JAMA. 2021.
- Wang Z, Schuetz EG, Xu Y, Thummel KE. Interplay between vitamin D and the drug metabolizing enzyme CYP3A4. J Steroid Biochem Mol Biol 2013;136:54-8. PubMed
- Doyle D, Browne U, Brickley A, Murphy D. Vitamin D-induced hypercalcaemia and acute kidney injury in sarcoidosis. BMJ Case Rep 2023;16(1):e250580. PubMed
- Williamson A, Martineau AR, Sheikh A, Jolliffe D, Griffiths CJ. Vitamin D for the management of asthma. Cochrane Database Syst Rev 2023;2(2):CD011511. PubMed
- Kinesya E, Santoso D, Gde Arya N, et al. Vitamin D as adjuvant therapy for diabetic foot ulcers: Systematic review and meta-analysis approach. Clin Nutr ESPEN 2023;54:137-143. PubMed
Zinc 88 references
- Barceloux DG. Zinc. J Toxicol Clin Toxicol 1999;37:279-92.
- Eby GA, Davis DR, Halcomb WW. Reduction in duration of common colds by zinc gluconate lozenges in a double-blind study. Antimicrob Agents Chemother 1984;25:20-4. DOI
- Smith DS, Helzner EC, Nuttall CE Jr, et al. Failure of zinc gluconate in treatment of acute upper respiratory tract infections. Antimicrob Agents Chemother 1989;33:646-8. PubMed
- Blondeau JM. Expanded activity and utility of the new fluoroquinolones: a review. Clin Ther 1999;21:3-40. PubMed
- Reyes AJ, Olhaberry JV, Leary WP, et al. Urinary zinc excretion, diuretics, zinc deficiency and some side-effects of diuretics. S Afr Med J 1983;64:936-41.
- Kugelmas M. Preliminary observation: oral zinc sulfate replacement is effective in treating muscle cramps in cirrhotic patients. J Am Coll Nutr 2000;19:13-5. PubMed
- Hebel SK, ed. Drug Facts and Comparisons. 52nd ed. St. Louis: Facts and Comparisons, 1998.
- Chan S, Gerson B, Subramaniam S. The role of copper, molybdenum, selenium, and zinc in nutrition and health. Clin Lab Med 1998;18:673-85. DOI
- Brewer GJ, Yuzbasiyan-Gurkan V, Johnson V, et al. Treatment of Wilson's disease with zinc: XI. Interaction with other anticopper agents. J Am Coll Nutr 1993;12:26-30. PubMed
- Fosmire GJ. Zinc toxicity. Am J Clin Nutr 1990;51:225-7.
- Lomaestro BM, Bailie GR. Absorption interactions with fluoroquinolones. 1995 update. Drug Saf 1995;12:314-33. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Seelig MS. Auto-immune complications of D-penicillamine - A possible result of zinc and magnesium depletion and of pyridoxine inactivation. J Am Coll Nutr 1982;1:207-14. PubMed
- Neuvonen PJ. Interactions with the absorption of tetracyclines. Drugs 1976;11:45-54.. PubMed
- Hirt M, Nobel S, Barron E. Zinc nasal gel for the treatment of common cold symptoms: A double-blind, placebo-controlled trial. Ear Nose Throat J 2000;79:778-82.. DOI
- Simkin PA. Oral zinc sulphate in rheumatoid arthritis. Lancet 1976;2:539-42. PubMed
- Wray D. A double-blind trial of systemic zinc sulfate in recurrent aphthous stomatitis. Oral Surg Oral Med Oral Pathol 1982;53:469-72. PubMed
- Douglas RM, Miles HB, Moore BW, et al. Failure of effervescent zinc acetate lozenges to alter the course of upper respiratory tract infections in Australian adults. Antimicrob Agents Chemother 1987;31:1263-5. PubMed
- Lagiou P, Wuu J, Trichopoulou A, et al. Diet and benign prostatic hyperplasia: a study in Greece. Urology 1999;54:284-90. PubMed
- Ewing CI, Gibbs AC, Ashcroft C, David TJ. Failure of oral zinc supplementation in atopic eczema. Eur J Clin Nutr 1991;45:507-10.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Age-Related Eye Disease Study Research Group. A randomized, placebo-controlled, clinical trial of high-dose supplementation with vitamins C and E, beta carotene, and zinc for age-related macular degeneration and vision loss. AREDS report no. 8. Arch Oph
- Greenberg JE, Lynn M, Kirsner RS, et al. Mucocutaneous pigmented macule as a result of zinc deposition. J Cutan Pathol 2002;29:613-5. PubMed
- Godfrey HR, Godfrey NJ, Godfrey JC, Riley D. A randomized clinical trial on the treatment of oral herpes with topical zinc oxide/glycine. Altern Ther Health Med 2001;7:49-56.
- Turner RB. Ineffectiveness of intranasal zinc gluconate for prevention of experimental rhinovirus colds. Clin Infect Dis 2001;33:1865-70. PubMed
- Belongia EA, Berg R, Liu K. A randomized trial of zinc nasal spray for the treatment of upper respiratory illness in adults. Am J Med 2001;111:103-8. PubMed
- Mossad SB. Effect of zincum gluconicum nasal gel on the duration and symptom severity of the common cold in otherwise healthy adults. QJM 2003;96:35-43. DOI
- Leitzmann MF, Stampfer MJ, Wu K, et al. Zinc supplement use and risk of prostate cancer. J Natl Cancer Inst 2003;95:1004-7.. PubMed
- Jafek BW, Linschoten M, Murrow BW. Zicam Induced Anosmia. American Rhinologic Society 49th Annual Fall Scientific Meeting abstract. Orlando, Florida. September 20, 2003. http://app.american-rhinologic.org/programs/2003ARSFallProgram071503.pdf (Accessed 24
- Uebayashi H, Hatanaka T, Kanemura F, Tonosaki K. Acute anosmia in the mouse: behavioral discrimination among the four basic taste substances. Physiol Behav 2001;72:291-6.. PubMed
- Barrett S. Zicam Marketers Sued. United States District Court Western District of Michigan Southern Division, Filed October 14, 2003, Case No. 4:03CV0146.
- Bilici M, Yildirim F, Kandil S, et al. Double-blind, placebo-controlled study of zinc sulfate in the treatment of attention deficit hyperactivity disorder. Prog Neuropsychopharmacol Biol Psychiatry 2004;28:181-90.. PubMed
- Polk RE, Healy DP, Sahai J, et al. Effect of ferrous sulfate and multivitamins with zinc on absorption of ciprofloxacin in normal volunteers. Antimicrob Agents Chemother 1989;33:1841-4. PubMed
- Mery C, Delrieu F, Ghozlan R, et al. Controlled trial of D-penicillamine in rheumatoid arthritis. Dose effect and the role of zinc. Scand J Rheumatol 1976;5:241-7. PubMed
- Penttila O, Hurme H, Neuvonen PJ. Effect of zinc sulfate on the absorption of tetracycline and doxycycline in man. Eur J Clin Pharmacol 1975;9:131-4.
- Kondo Y, Yamagata K, Satoh M, et al. Optimal administration schedule of cisplatin for bladder tumor with minimal induction of metallothionein. J Urol 2003;170:2467-70. PubMed
- Doz F, Berens ME, Deschepper CF, et al. Experimental basis for increasing the therapeutic index of cis-diamminedicarboxylatocyclobutaneplatinum(II) in brain tumor therapy by a high-zinc diet. Cancer Chemother Pharmacol 1992;29:219-26.
- Wester PO. Urinary zinc excretion during treatment with different diuretics. Acta Med Scand 1980;208:209-12. PubMed
- Golik A, Modai D, Weissgarten J, et al. Hydrochlorothiazide-amiloride causes excessive urinary zinc excretion. Clin Pharmacol Ther 1987;42:42-4. PubMed
- Leary WP, Reyes AJ, Van der Byl K. Urinary magnesium and zinc excretion after two different single doses of amiloride in healthy adults. Curr Ther Res 1983;34:205-16.
- McBride K, Slotnick B, Margolis FL. Does intranasal application of zinc sulfate produce anosmia in the mouse? An olfactometric and anatomical study. Chem Senses 2003;28:659-70. PubMed
- Burd GD. Morphological study of the effects of intranasal zinc sulfate irrigation on the mouse olfactory epithelium and olfactory bulb. Microsc Res Tech 1993;24:195-213. PubMed
- Ducray A, Bondier JR, Michel G, et al. Recovery following peripheral destruction of olfactory neurons in young and adult mice. Eur J Neurosci 2002;15:1907-17. PubMed
- Mayer AD, Rosenblatt JS. Peripheral olfactory deafferentation of the primary olfactory system in rats using ZnSO4 nasal spray with special reference to maternal behavior. Physiol Behav 1993;53:587-92. PubMed
- DeCook CA, Hirsch AR. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Tisdall FF, Brown A, Defries RD. Persistent anosmia following zinc sulfate nasal spraying. JPed 1938;18:60-2. DOI
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Public Health Advisory. Loss of sense of smell with intranasal cold remedies containing zinc. U.S. Food and Drug Administration, June 16, 2009. Available at: http://www.fda.gov/Drugs/DrugSafety/PublicHealthAdvisories/ucm166059.htm (Accessed 16 June 2009)
- Dooren JC. FDA warns against use of Zicam. The Wall Street Journal, June 16, 2009. Available at: http://online.wsj.com/article/SB124516778692319231.html#mod=djemHL?mg=com-wsj (Accessed 16 June 2009).
- Alexander TH, Davidson TM. Intranasal zinc and anosmia: the zinc-induced anosmia syndrome. Laryngoscope 2006;116:217-20.
- Health Canada / GlaxoSmithKline Consumer Healthcare. Association of long-term, excessive use of zinc-containing Poli-Grip products with myeloneuropathy and blood dyscrasias. February 18, 2010. Available at: http://hc-sc.gc.ca/dhp-mps/alt_formats/pdf/medef
- GlaxoSmithKline Consumer Advisory. GlaxoSmithKline (GSK) warns about a potential health risk associated with long-term, excessive use of GSK's zinc-containing denture adhesives Super Polygrip Original, Ultra Fresh and Extra Care. February 18, 2010. Availa
- Science M, Johnstone J, Roth DE, et al. Zinc for the treatment of the common cold: a systematic review and meta-analysis of randomized controlled trials. CMAJ 2012;184:E551-61. PubMed
- Castilla-Higuero, L., Romero-Gomez, M., Suarez, E., and Castro, M. Acute hepatitis after starting zinc therapy in a patient with presymptomatic Wilson's disease. Hepatology 2000;32(4 Pt 1):877. PubMed
- Sharquie, K. E., Najim, R. A., Farjou, I. B., and Al Timimi, D. J. Oral zinc sulphate in the treatment of acute cutaneous leishmaniasis. Clin.Exp.Dermatol. 2001;26(1):21-26. PubMed
- Dreno, B., Moyse, D., Alirezai, M., Amblard, P., Auffret, N., Beylot, C., Bodokh, I., Chivot, M., Daniel, F., Humbert, P., Meynadier, J., and Poli, F. Multicenter randomized comparative double-blind controlled clinical trial of the safety and efficacy of
- Moore, R. Bleeding gastric erosion after oral zinc sulphate. Br.Med J 3-25-1978;1(6115):754. PubMed
- Jafek, B. W., Linschoten, M. R., and Murrow, B. W. Anosmia after intranasal zinc gluconate use. Am J Rhinol. 2004;18(3):137-141. DOI
- Simonart, T. and de, Maertelaer, V. Systemic treatments for cutaneous warts: a systematic review. J Dermatolog.Treat. 2012;23(1):72-77. PubMed
- Cochran, R. J., Tucker, S. B., and Flannigan, S. A. Topical zinc therapy for acne vulgaris. Int.J Dermatol. 1985;24(3):188-190. DOI
- Morgan, A. A. Bleeding gastric erosion after oral zinc sulphate. Br.Med.J. 5-13-1978;1(6122):1283-1284. PubMed
- Murphy, J. V. Intoxication following ingestion of elemental zinc. JAMA 6-22-1970;212(12):2119-2120.
- Lang, C. J., Rabas-Kolominsky, P., Engelhardt, A., Kobras, G., and Konig, H. J. Fatal deterioration of Wilson's disease after institution of oral zinc therapy. Arch Neurol. 1993;50(10):1007-1008. PubMed
- Fjellner, B. Drug-induced lupus erythematosus aggravated by oral zinc therapy. Acta Derm.Venereol. 1979;59(4):368-370. DOI
- Varas Lorenzo, M. J. Zinc acexamate and ranitidine in the short- and mid-term management of gastroduodenal ulcers. Curr Ther Res 21986;39:19-29.
- Bosch, F. and Jimenez, E. Post-marketing surveillance of zinc acexamate in peptic ulcer treatment. Clin Trials J 1990;27:301-312.
- DeCook, C. A. and Hirsch, A. R. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Crown LA, May JA. Zinc toxicity: denture adhesives, bone marrow failure and polyneuropathy. Tenn Med. 2012 Feb;105(2):39-40, 42.
- Dadamio J, Van Tournout M, Teughels W, Dekeyser C, Coucke W, Quirynen M. Efficacy of different mouthrinse formulations in reducing oral malodour: a randomized clinical trial. J Clin Periodontol. 2013 May;40(5):505-13. PubMed
- Moyle G, Else L, Jackson A, Back D, Yapa MH, Seymour N, Ringner-Nackter L, Karolia Z, Gazzard B, Boffito M. Coadministration of atazanavir-ritonavir and zinc sulfate: impact on hyperbilirubinemia and pharmacokinetics. Antimicrob Agents Chemother. 2013 Aug PubMed
- Zittel S, Ufer F, Gerloff C, Münchau A, Rosenkranz M. Severe myelopathy after denture cream use--is copper deficiency or excess zinc the cause? Clin Neurol Neurosurg. 2014 Jun;121:17-8. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Guidelines for the Use of Antiretroviral Agents in HIV-1-Infected Adults and Adolescents: Drug Interactions between Integrase Inhibitors and Other Drugs. AIDSinfo. July 14, 2016. Available at: https://aidsinfo.nih.gov/guidelines/html/1/adult-and-adolescen
- Ding Y, Jia YY, Li F, et al. The effect of staggered administration of zinc sulfate on the pharmacokinetics of oral cephalexin. Br J Clin Pharmacol. 2012 Mar;73(3):422-7. PubMed
- Fallah R, Sabbaghzadegan S, Karbasi SA, Binesh F. Efficacy of zinc sulfate supplement on febrile seizure recurrence prevention in children with normal serum zinc level: A randomised clinical trial. Nutrition. 2015;31(11-12):1358-61. PubMed
- Lazzerini M, Wanzira H. Oral zinc for treating diarrhoea in children. Cochrane Database Syst Rev. 2016;12:CD005436. PubMed
- Mahmoud AM, Al-Alem U, Dabbous F, et al. Zinc intake and risk of prostate cancer: Case-control study and meta-analysis. PLoS One. 2016;11(11):e0165956. PubMed
- Nagraj SK, George RP, Shetty N, Levenson D, Ferraiolo DM, Shrestha A. Interventions for managing taste disturbances. Cochrane Database Syst Rev. 2017 Dec 20;12(12):CD010470. PubMed
- Yee BE, Richards P, Sui JY, Marsch AF. Serum zinc levels and efficacy of zinc treatment in acne vulgaris: A systematic review and meta-analysis. Dermatol Ther. 2020:e14252. PubMed
- Janyajirawong R, Vilaichone RK, Sethasine S. Efficacy of zinc supplement in minimal hepatic encephalopathy: A prospective, randomized controlled study (Zinc-MHE Trial). Asian Pac J Cancer Prev 2021;22(9):2879-2887. PubMed
- Nakano M, Nakamura Y, Miyazaki A, Takahashi J. Zinc pharmacotherapy for elderly osteoporotic patients with zinc deficiency in a clinical setting. Nutrients 2021;13(6):1814. PubMed
- Tolino E, Skroza N, Mambrin A, et al. An open-label study comparing oral zinc to lymecycline in the treatment of acne vulgaris. J Clin Aesthet Dermatol 2021;14(5):56-58.
- Hunter J, Arentz S, Goldenberg J, et al. Zinc for the prevention or treatment of acute viral respiratory tract infections in adults: a rapid systematic review and meta-analysis of randomised controlled trials. BMJ Open. 2021;11(11):e047474. PubMed
- Yamazaki K, Kageyama H, Fujiyama T, Ito T, Urano S, Honda T. A case of systemic contact dermatitis due to zinc supplements. Int J Dermatol 2022. PubMed
- Magham K, Han J, Eilbert W, Bunney EB. Severe copper deficiency anemia caused by zinc supplement use. Am J Emerg Med 2023;72:222. PubMed
- Sivakumar RR, Chinnaiah Govindareddy D, Sahoo J, Bobby Z, Chinnakali P. Effect of daily zinc supplementation for 12 weeks on serum thyroid auto-antibody levels in children and adolescents with autoimmune thyroiditis - a randomized controlled trial. J Pedi PubMed
- AlDhasee O, AlMalki H, AlKharashi N, AlJeraisy N, Al Deeb M. Acute zinc sulfate overdose: clinical presentation and management. BMJ Case Rep 2025;18(1):e263899. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Niacin 66 references
- Garg R, Malinow MR, Pettinger M, et al. Niacin treatment increases plasma homocysteine levels. Am Heart J 1999;138:1082-7.
- Anon. Inositol hexaniacinate. Altern Med Rev 1998;3:222-3.
- Knodel LC, Talbert RL. Adverse effects of hypolipidaemic drugs. Med Toxicol 1987;2:10-32. PubMed
- Guyton JR, Blazing MA, Hagar J, et al. Extended-release niacin vs gemfibrozil for the treatment of low levels of high-density lipoprotein cholesterol. Niaspan-Gemfibrozil Study Group. Arch Intern Med 2000;160:1177-84. PubMed
- Gibbons LW, Gonzalez V, Gordon N, Grundy S. The prevalence of side effects with regular and sustained-release nicotinic acid. Am J Med 1995;99:378-85. PubMed
- Whelan AM, Price SO, Fowler SF, Hainer BL. The effect of aspirin on niacin-induced cutaneous reactions. J Fam Pract 1992;34:165-8.
- Jungnickel PW, Maloley PA, Vander Tuin EL, et al. Effect of two aspirin pretreatment regimens on niacin-induced cutaneous reactions. J Gen Intern Med 1997;12:591-6. PubMed
- Capuzzi DM, Guyton JR, Morgan JM, et al. Efficacy and safety of an extended-release niacin (Niaspan): a long-term study. Am J Cardiol 1998;82:74-81;disc. 85U-6U. PubMed
- Gray DR, Morgan T, Chretien SD, Kashyap ML. Efficacy and safety of controlled-release niacin in dyslipoproteinemic veterans. Ann Intern Med 1994;121:252-8. PubMed
- McKenney JM, Proctor JD, Harris S, Chinchili VM. A comparison of the efficacy and toxic effects of sustained- vs immediate-release niacin in hypercholesterolemic patients. JAMA 1994;271:672-7. DOI
- Knopp RH, Alagona P, Davidson M, et al. Equivalent efficacy of a time-release form of niacin (Niaspan) given once-a-night versus plain niacin in the management of hyperlipidemia. Metabolism 1998;47:1097-104. PubMed
- Knopp RH. Clinical profiles of plain versus sustained-release niacin (Niaspan) and the physiologic rationale for nighttime dosing. Am J Cardiol 1998;82:24U-28U;discussion 39U-41U. PubMed
- Garg A, Grundy SM. Nicotinic acid as therapy for dyslipidemia in non-insulin-dependent diabetes mellitus. JAMA 1990;264:723-6. DOI
- Leighton RF, Gordon NF, Small GS, et al. Dental and gingival pain as side effects of niacin therapy. Chest 1998;114:1472-4. PubMed
- American Society of Health-System Pharmacists. ASHP Therapeutic Position Statement on the safe use of niacin in the management of dyslipidemias. Am J Health Syst Pharm 1997;54:2815-9. DOI
- Vega GL, Grundy SM. Lipoprotein responses to treatment with lovastatin, gemfibrozil, and nicotinic acid in normolipidemic patients with hypoalphalipoproteinemia. Arch Intern Med 1994;154:73-82. DOI
- Guyton JR, Goldberg AC, Kreisberg RA, et al. Effectiveness of once-nightly dosing of extended-release niacin alone and in combination for hypercholesterolemia. Am J Cardiol 1998;82:737-43.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Bays HE, Dujovne CA. Drug interactions of lipid-altering drugs. Drug Saf 1998;19:355-71. PubMed
- Rader JI, Calvert RJ, Hathcock JN. Hepatic toxicity of unmodified and time-release preparations of niacin. Am J Med 1992;92:77-81. PubMed
- Kahn SE, Beard JC, Schwartz MW, et al. Increased B-cell secretory capacity as mechanism for islet adaptation to nicotinic acid-induced insulin resistance. Diabetes 1989;38:562-8.
- Schwartz ML. Severe reversible hyperglycemia as a consequence of niacin therapy. Arch Int Med 1993;153:2050-2. DOI
- Raising HDL and Niacin Use. Pharmacist's Letter/Prescriber's Letter 2004;20(5):200504.
- McKenney J. New perspectives on the use of niacin in the treatment of lipid disorders. Arch Intern Med 2004;164:697-705. PubMed
- Reaven P, Witztum JL. Lovastatin, nicotinic acid and rhabdomyolysis (letter). Ann Int Med 1988;109:597-8. PubMed
- Ito MK. Advances in the understanding and management of dyslipidemia: using niacin-based therapies. Am J Health-Syst Pharm 2003;60(suppl 2):s15-21. PubMed
- Schwab RA, Bachhuber BH. Delirium and lactic acidosis caused by ethanol and niacin coingestion. Am J Emerg Med 1991;9:363-5. PubMed
- Product information: Niaspan. Kos Pharmaceuticals. Cranbury, NJ. 2005. Available at www.niaspan.com/professional/content/pdfs/productinfo.pdf. (Accessed 3 March 2006).
- Ding RW, Kolbe K, Merz B, et al. Pharmacokinetics of nicotinic acid-salicylic acid interaction. Clin Pharmacol Ther 1989;46:642-7. PubMed
- NIH News. NIH stops clinical trial on combination cholesterol treatment. May 26, 2011. http://www.nih.gov/news/health/may2011/nhlbi-26.htm. (Accessed 3 June 2011).
- Dearing BD, Lavie CJ, Lohmann TP, Genton E. Niacin-induced clotting factor synthesis deficiency with coagulopathy. Arch Intern Med. 1992;152(4):861-3. DOI
- O'Brien T, Silverberg JD, Nguyen TT. Nicotinic acid-induced toxicity associated with cytopenia and decreased levels of thyroxine-binding globulin. Mayo Clin Proc. 1992;67(5):465-8. PubMed
- Gadegbeku CA, Dhandayuthapani A, Shrayyef MZ, Egan BM. Hemodynamic effects of nicotinic acid infusion in normotensive and hypertensive subjects. Am J Hypertens. 2003;16(1):67-71. PubMed
- Garnett WR. Interactions with hydroxymethylglutaryl-coenzyme A reductase inhibitors. Am J Health Syst Pharm. 1995;52(15):1639-45. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Dunn RT, Ford MA, Rindone JP, Kwiecinski FA. Low-Dose Aspirin and Ibuprofen Reduce the Cutaneous Reactions Following Niacin Administration. Am J Ther. 1995;2(7):478-480. PubMed
- Cashin-Hemphill L, Spencer CA, Nicoloff JT, et al. Alterations in serum thyroid hormonal indices with colestipol-niacin therapy. Ann Intern Med. 1987;107(3):324-9. PubMed
- Drinka PJ. Alterations in thyroid and hepatic function tests associated with preparations of sustained-release niacin. Mayo Clin Proc. 1992;67(12):1206. PubMed
- Shakir KM, Kroll S, Aprill BS, Drake AJ 3rd, Eisold JF. Nicotinic acid decreases serum thyroid hormone levels while maintaining a euthyroid state. Mayo Clin Proc. 1995;70(6):556-8. PubMed
- Etchason JA, Miller TD, Squires RW, et al. Niacin-induced hepatitis: a potential side effect with low-dose time-release niacin. Mayo Clin Proc. 1991;66(1):23-8. PubMed
- Henkin Y, Johnson KC, Segrest JP. Rechallenge with crystalline niacin after drug-induced hepatitis from sustained-release niacin. JAMA. 1990;264(2):241-3. DOI
- Henkin Y, Oberman A, Hurst DC, Segrest JP. Niacin revisited: clinical observations on an important but underutilized drug. Am J Med. 1991;91(3):239-46. PubMed
- Brown BG, Bardsley J, Poulin D, et al. Moderate dose, three-drug therapy with niacin, lovastatin, and colestipol to reduce low-density lipoprotein cholesterol <100 mg/dl in patients with hyperlipidemia and coronary artery disease. Am J Cardiol. 1997;80(2)
- Goldberg A, Alagona P Jr, Capuzzi DM, et al. Multiple-dose efficacy and safety of an extended-release form of niacin in the management of hyperlipidemia. Am J Cardiol. 2000;85(9):1100-5. PubMed
- Aronov DM, Keenan JM, Akhmedzhanov NM, et al. Clinical trial of wax-matrix sustained-release niacin in a Russian population with hypercholesterolemia. Arch Fam Med. 1996;5(10):567-75. PubMed
- Morgan JM, Capuzzi DM, Guyton JR, et al. Treatment Effect of Niaspan, a Controlled-release Niacin, in Patients With Hypercholesterolemia: A Placebo-controlled Trial. J Cardiovasc Pharmacol Ther. 1996;1(3):195-202. PubMed
- Andersson RG, Aberg G, Brattsand R, Ericsson E, Lundholm L. Studies on the mechanism of flush induced by nicotinic acid. Acta Pharmacol Toxicol (Copenh). 1977 Jul;41(1):1-10. PubMed
- Brown WV. Niacin for lipid disorders. Indications, effectiveness, and safety. Postgrad Med. 1995 Aug;98(2):185-9, 192-3. PubMed
- O'REILLY PO, CALLBECK MJ, HOFFER A. Sustained-release nicotinic acid (nicospan); effect on (1) cholesterol levels and (2) leukocytes. Can Med Assoc J. 1959;80(5):359-62.
- Gharavi AG, Diamond JA, Smith DA, Phillips RA. Niacin-induced myopathy. Am J Cardiol. 1994;74(8):841-2. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Fraunfelder FW, Fraunfelder FT, Illingworth DR. Adverse ocular effects associated with niacin therapy. Br J Ophthalmol 1995;79:54-56. PubMed
- Ali EH, McJunkin B, Jubelirer S, Hood W. Niacin induced coagulopathy as a manifestation of occult liver injury. W V Med J. 2013 Jan-Feb;109(1):12-4
- Aramwit P, Srisawadwong R, Supasyndh O. Effectiveness and safety of extended-release nicotinic acid for reducing serum phosphorus in hemodialysis patients. J Nephrol. 2012 May-Jun;25(3):354-62. PubMed
- Bassan M. A case for immediate-release niacin. Heart Lung. 2012 Jan-Feb;41(1):95-8. PubMed
- Davidson MH, Rooney M, Pollock E, Drucker J, Choy Y. Effect of colesevelam and niacin on low-density lipoprotein cholesterol and glycemic control in subjects with dyslipidemia and impaired fasting glucose. J Clin Lipidol. 2013 Sep-Oct;7(5):423-32. PubMed
- Guyton JR, Fazio S, Adewale AJ, Jensen E, Tomassini JE, Shah A, Tershakovec AM. Effect of extended-release niacin on new-onset diabetes among hyperlipidemic patients treated with ezetimibe/simvastatin in a randomized controlled trial. Diabetes Care. 2012 PubMed
- Loebl T, Raskin S. A novel case report: acute manic psychotic episode after treatment with niacin. J Neuropsychiatry Clin Neurosci. 2013 Fall;25(4):E14. PubMed
- Teo KK, Goldstein LB, Chaitman BR, Grant S, Weintraub WS, Anderson DC, Sila CA, Cruz-Flores S, Padley RJ, Kostuk WJ, Boden WE; AIM-HIGH Investigators. Extended-release niacin therapy and risk of ischemic stroke in patients with cardiovascular disease: the
- Goldie C, Taylor AJ, Nguyen P, McCoy C, Zhao XQ, Preiss D. Niacin therapy and the risk of new-onset diabetes: a meta-analysis of randomized controlled trials. Heart. 2016 Feb;102(3):198-203.
- Schandelmaier S, Briel M, Saccilotto R, Olu KK, Arpagaus A, Hemkens LG, Nordmann AJ. Niacin for primary and secondary prevention of cardiovascular events. Cochrane Database Syst Rev. 2017 Jun 14;6:CD009744. PubMed
- Jenkins DJA, Spence JD, Giovannucci EL, et al. Supplemental vitamins and minerals for CVD prevention and treatment. J Am Coll Cardiol 2018;71(22):2570-84. PubMed
- Song S, Lee CJ, Oh J, Park S, Kang SM, Lee SH. Effect of Niacin on Carotid Atherosclerosis in Patients at Low-Density Lipoprotein-Cholesterol Goal but High Lipoprotein (a) Level: a 2-Year Follow-Up Study. J Lipid Atheroscler. 2019;8(1):58-66. PubMed
- Kimura H, Umemori Y, Yuki D. Anaphylactic shock-like symptoms due to niacin overdose: A case report. J Dermatol 2022;49(8):e287-e288. PubMed
- Nawaz N, Mistretta T, Karime C, Lewis J, Wolf E. Cholestatic Drug-Induced Liver Injury in a Patient Taking High-Dose Niacin for Hyperlipidemia. J Investig Med High Impact Case Rep 2024;12:23247096231224349. PubMed
Ginkgo 97 references
- Davydov L, Stirling AL. Stevens-Johnson syndrome with Ginkgo biloba. J Herb Pharmacother 2001;1:65-9. DOI
- Benjamin J, Muir T, Briggs K, Pentland B. A case of cerebral haemorrhage-can Ginkgo biloba be implicated? Postgrad Med J 2001;77:112-3.
- Matthews, MK. Association of Ginkgo biloba with intracerebral hemorrhage. Neurology 1998;50:1934.
- Rowin J, Lewis SL. Spontaneous bilateral subdural hemotomas with chronic Ginkgo biloba ingestion. Neurology 1996;46:1775-6.
- Rosenblatt M, Mindel T. Spontaneous hyphema associated with ingestion of Ginkgo biloba extract. N Engl J Med 1997;336:1108.
- Fessenden JM, Wittenborn W, Clarke L. Gingko biloba: a case report of herbal medicine and bleeding postoperatively from a laparoscopic cholecystectomy. Am Surg 2001;67:33-5. DOI
- Gurley BJ, Gardner SF, Hubbard MA. Clinical assessment of potential cytochrome P450-mediated herb-drug interactions. AAPS Ann Mtg & Expo Indianapolis, IN: 2000; Oct 29 - Nov 2:presentation #3460.
- Cohen AJ, Bartlik B. Ginkgo biloba for antidepressant-induced sexual dysfunction. J Sex Marital Ther 1998;24:139-43. PubMed
- Kudolo GB. The effect of 3-month ingestion of Ginkgo biloba extract on pancreatic beta-cell function in response to glucose loading in normal glucose tolerant individuals. J Clin Pharmacol 2000;40:647-54.
- Heck AM, DeWitt BA, Lukes AL. Potential interactions between alternative therapies and warfarin. Am J Health Syst Pharm 2000;57:1221-7. DOI
- Cesarani A, Meloni F, Alpini D, et al. Ginkgo biloba (EGb 761) in the treatment of equilibrium disorders. Adv Ther 1998;15:291-304.
- Galluzzi S, Zanetti O, Binetti G, et al. Coma in a patient with Alzheimer's disease taking low dose trazodone and Ginkgo biloba. J Neurol Neurosurg Psychiatry 2000;68:679-80. DOI
- Budzinski JW, Foster BC, Vandenhoek S, Arnason JT. An in vitro evaluation of human cytochrome P450 3A4 inhibition by selected commercial herbal extracts and tinctures. Phytomedicine 2000;7:273-82. PubMed
- Gregory PJ. Seizure associated with Ginkgo biloba? Ann Intern Med 2001;134:344.
- Granger AS. Ginkgo biloba precipitating epileptic seizures. Age Ageing 2001;30:523-5. PubMed
- Kajiyama Y, Fujii K, Takeuchi H, Manabe Y. Ginkgo seed poisoning. Pediatrics 2002;109:325-7. PubMed
- Miwa H, Iijima M, Tanaka S, Mizuno Y. Generalized convulsions after consuming a large amount of gingko nuts. Epilepsia 2001;42:280-1. DOI
- Burschka MA, Hassan HA, Reineke T, et al. Effect of treatment with Ginkgo biloba extract EGb 761 (oral) on unilateral idiopathic sudden hearing loss in a prospective randomized double-blind study of 106 outpatients. Eur Arch Otorhinolaryngol 2001;258:213- PubMed
- Miller LG, Freeman B. Possible subdural hematoma associated with Ginkgo biloba. J Herb Pharmacother 2002;2:57-63.
- Kudolo GB, Dorsey S, Blodgett J. Effect of the ingestion of Ginkgo biloba extract on platelet aggregation and urinary prostanoid excretion in healthy and Type 2 diabetic subjects. Thromb Res 2002;108:151-60.. PubMed
- Fong KC, Kinnear PE. Retrobulbar haemorrhage associated with chronic Ginkgo biloba ingestion. Postgrad Med J 2003;79:531-2..
- Gurley BJ, Gardner SF, Hubbard MA, et al. Cytochrome P450 phenotypic ratios for predicting herb-drug interactions in humans. Clin Pharmacol Ther 2002;72:276-87.. PubMed
- Kang BJ, Lee SJ, Kim MD, Cho MJ. A placebo-controlled, double-blind trial of Ginkgo biloba for antidepressant-induced sexual dysfunction. Hum Psychopharmacol 2002;17:279-84.
- Yale SH, Glurich I. Analysis of the inhibitory potential of Ginkgo biloba, Echinacea purpurea, and Serenoa repens on the metabolic activity of cytochrome P450 3A4, 2D6, and 2C9. J Altern Complement Med 2005;11:433-9.
- Yasui-Furukori N, Furukori H, Kaneda A, et al. The effects of Ginkgo biloba extracts on the pharmacokinetics and pharmacodynamics of donepezil. J Clin Pharmacol 2004;44:538-42.
- Markowitz JS, Donovan JL, Lindsay DeVane C, et al. Multiple-dose administration of Ginkgo biloba did not affect cytochrome P-450 2D6 or 3A4 activity in normal volunteers. J Clin Psychopharmacol 2003;23:576-81. PubMed
- Arenz A, Kelin M, Flehe K, et al. Occurrence of neurotoxic 4'-O-methylpyridoxine in ginkgo biloba leaves, ginkgo medications and Japanese ginkgo food. Planta Med 1996;62:548-51.
- Engelsen J, Nielsen JD, Winther K. Effect of coenzyme Q10 and Ginkgo biloba on warfarin dosage in stable, long-term warfarin treated outpatients. A randomised, double blind, placebo-crossover trial. Thromb Haemost 2002;87:1075-6. DOI
- Gaudineau C, Beckerman R, Welbourn S, Auclair K. Inhibition of human P450 enzymes by multiple constituents of the Ginkgo biloba extract. Biochem Biophys Res Comm 2004;318:1072–8. PubMed
- Kohler S, Funk P, Kieser M. Influence of a 7-day treatment with Ginkgo biloba special extract EGb 761 on bleeding time and coagulation: a randomized, placebo-controlled, double-blind study in healthy volunteers. Blood Coagul Fibrinolysis 2004;15:303–9. PubMed
- Jiang X, Williams KM, Liauw WS, et al. Effect of ginkgo and ginger on the pharmacokinetics and pharmacodynamics of warfarin in healthy subjects. Br J Clin Pharmacol 2005;59:425-32. PubMed
- Destro MW, Speranzini MB, Cavalheiro Filho C, et al. Bilateral haematoma after rhytidoplasty and blepharoplasty following chronic use of Ginkgo biloba. Br J Plast Surg 2005;58:100-1. PubMed
- Yin OQ, Tomlinson B, Waye MM, et al. Pharmacogenetics and herb-drug interactions: experience with Ginkgo biloba and omeprazole. Pharmacogenetics 2004;14:841-50. PubMed
- Bent S, Goldberg H, Padula A, Avins AL. Spontaneous bleeding associated with Ginkgo biloba: a case report and systematic review of the literature. J Gen Intern Med 2005;20;657-61. DOI
- Meisel C, Johne A, Roots I. Fatal intracerebral mass bleeding associated with Ginkgo biloba and ibuprofen. Atherosclerosis 2003;167:367. PubMed
- Bebbington A, Kulkarni R, Roberts P. Ginkgo biloba: Persistent bleeding after total hip arthroplasty caused by herbal self-medication. J Arthroplasty 2005;20:125-6. .
- Kupiec T, Raj V. Fatal seizures due to potential herb-drug interactions with Ginkgo biloba. J Anal Toxicol 2005:755-8. PubMed
- Hauser D, Gayowski T, Singh N. Bleeding complications precipitated by unrecognized Gingko biloba use after liver transplantation. Transpl Int 2002;15:377-9. DOI
- Mohutsky MA, Anderson GD, Miller JW, Elmer GW. Ginkgo biloba: evaluation of CYP2C9 drug interactions in vitro and in vivo. Am J Ther 2006;13:24-31. PubMed
- Kudolo GB. The effect of 3-month ingestion of Ginkgo biloba extract (EGb 761) on pancreatic beta-cell function in response to glucose loading in individuals with non-insulin-dependent diabetes mellitus. J Clin Pharmacol 2001;41:600-11.
- Pennisi RS. Acute generalised exanthematous pustulosis induced by the herbal remedy Ginkgo biloba. Med J Aust 2006;184:583-4. PubMed
- Yagmur E, Piatkowski A, Groger A, et al. Bleeding complication under Gingko biloba medication. Am J Hematol 2005;79:343-4. PubMed
- Vale S. Subarachnoid haemorrhage associated with Ginkgo biloba. Lancet 1998;352:36. PubMed
- Aruna D, Naidu MU. Pharmacodynamic interaction studies of Ginkgo biloba with cilostazol and clopidogrel in healthy human subjects. Br J Clin Pharmacol 2007;63:333-8.
- Dugoua JJ, Mills E, Perri D, Koren G. Safety and efficacy of ginkgo (Ginkgo biloba) during pregnancy and lactation. Can J Clin Pharmacol 2006;13:e277-84.
- Jiang X, Blair EY, McLachlan AJ. Investigation of the effects of herbal medicines on warfarin response in healthy subjects: a population pharmacokinetic-pharmacodynamic modeling approach. J Clin Pharmacol 2006;46:1370-8. PubMed
- Woelk H, Arnoldt KH, Kieser M, Hoerr R. Ginkgo biloba special extract EGb 761 in generalized anxiety disorder and adjustment disorder with anxious mood: a randomized, double-blind, placebo-controlled trial. J Psychiatr Res 2007;41:472-80. PubMed
- DeKosky ST, Williamson JD, Fitzpatrick AL, et al. Ginkgo biloba for prevention of dementia. JAMA 2008;300:2253-62.
- Dodge HH, Zitzelberger T, Oken BS, et al. A randomized placebo-controlled trial of ginkgo biloba for the prevention of cognitive decline. Neurology 2008;70(19 Pt 2):1809-17. PubMed
- Wiegman DJ, Brinkman K, Franssen EJ. Interaction of Ginkgo biloba with efavirenz. AIDS 2009;23:1184-5. PubMed
- Kim BH, Kim KP, Lim KS, et al. Influence of Ginkgo biloba extract on the pharmacodynamic effects and pharmacokinetic properties of ticlopidine: An open-label, randomized, two-period, two-treatment, two-sequence, single-dose crossover study in healthy Kor
- Salehi B, Imani R, Mohammadi MR, et al. Ginkgo biloba for attention-deficit/hyperactivity disorder in children and adolescents: a double blind, randomized controlled trial. Prog Neuropsychopharmacol Biol Psychiatry 2010;34:76-80. PubMed
- Kellermann AJ, Kloft C. Is there a risk of bleeding associated with standardized ginkgo biloba extract therapy? A systematic review and meta-analysis. Pharmacotherapy 2011;31:490-502.
- Kuller LH, Ives DG, Fitzpatrick AL, et al. Does Ginkgo biloba reduce the risk of cardiovascular events? Circ Cardiovasc Qual Outcomes 2010;3:41-7.
- Naccarato M, Yoong D, Gough K. A potential drug-herbal interaction between Ginkgo biloba and efavirenz. J Int Assoc Physicians AIDS Care (Chic). 2012;11(2):98-100. doi: 10.1177/1545109711435364. Epub 2012 Feb 9.
- Engelsen, J., Nielsen, J. D., and Hansen, K. F. [Effect of Coenzyme Q10 and Ginkgo biloba on warfarin dosage in patients on long-term warfarin treatment. A randomized, double-blind, placebo-controlled cross-over trial]. Ugeskr.Laeger 4-28-2003;165(18):18
- Parsad, D., Pandhi, R., and Juneja, A. Effectiveness of oral Ginkgo biloba in treating limited, slowly spreading vitiligo. Clin Exp.Dermatol. 2003;28(3):285-287.
- Bal Dit, Sollier C., Caplain, H., and Drouet, L. No alteration in platelet function or coagulation induced by EGb761 in a controlled study. Clin Lab Haematol. 2003;25(4):251-253. PubMed
- Yoshioka, M., Ohnishi, N., Koishi, T., Obata, Y., Nakagawa, M., Matsumoto, T., Tagagi, K., Takara, K., Ohkuni, T., Yokoyama, T., and Kuroda, K. Studies on interactions between functional foods or dietary supplements and medicines. IV. Effects of ginkgo b
- Yoshioka, M., Ohnishi, N., Sone, N., Egami, S., Takara, K., Yokoyama, T., and Kuroda, K. Studies on interactions between functional foods or dietary supplements and medicines. III. Effects of ginkgo biloba leaf extract on the pharmacokinetics of nifedipi
- Lovera, J., Bagert, B., Smoot, K., Morris, C. D., Frank, R., Bogardus, K., Wild, K., Oken, B., Whitham, R., and Bourdette, D. Ginkgo biloba for the improvement of cognitive performance in multiple sclerosis: a randomized, placebo-controlled trial. Mult.S PubMed
- Lin, Y. Y., Chu, S. J., and Tsai, S. H. Association between priapism and concurrent use of risperidone and Ginkgo biloba. Mayo Clin Proc 2007;82(10):1289-1290.
- Robertson, S. M., Davey, R. T., Voell, J., Formentini, E., Alfaro, R. M., and Penzak, S. R. Effect of Ginkgo biloba extract on lopinavir, midazolam and fexofenadine pharmacokinetics in healthy subjects. Curr Med Res Opin 2008;24(2):591-599. PubMed
- Penzak, S. R., Busse, K. H., Robertson, S. M., Formentini, E., Alfaro, R. M., and Davey, R. T., Jr. Limitations of using a single postdose midazolam concentration to predict CYP3A-mediated drug interactions. J Clin Pharmacol 2008;48(6):671-680. PubMed
- May, B. H., Yang, A. W., Zhang, A. L., Owens, M. D., Bennett, L., Head, R., Cobiac, L., Li, C. G., Hugel, H., Story, D. F., and Xue, C. C. Chinese herbal medicine for Mild Cognitive Impairment and Age Associated Memory Impairment: a review of randomised
- Choi, W. S., Choi, C. J., Kim, K. S., Lee, J. H., Song, C. H., Chung, J. H., Ock, S. M., Lee, J. B., and Kim, C. M. To compare the efficacy and safety of nifedipine sustained release with Ginkgo biloba extract to treat patients with primary Raynaud's phe
- Lei, H. P., Wang, G., Wang, L. S., Ou-yang, D. S., Chen, H., Li, Q., Zhang, W., Tan, Z. R., Fan, L., He, Y. J., and Zhou, H. H. Lack of effect of Ginkgo biloba on voriconazole pharmacokinetics in Chinese volunteers identified as CYP2C19 poor and extensiv
- Russo, V., Stella, A., Appezzati, L., Barone, A., Stagni, E., Roszkowska, A., and Delle, Noci N. Clinical efficacy of a Ginkgo biloba extract in the topical treatment of allergic conjunctivitis. Eur J Ophthalmol. 2009;19(3):331-336. PubMed
- Fan, L., Tao, G. Y., Wang, G., Chen, Y., Zhang, W., He, Y. J., Li, Q., Lei, H. P., Jiang, F., Hu, D. L., Huang, Y. F., and Zhou, H. H. Effects of Ginkgo biloba extract ingestion on the pharmacokinetics of talinolol in healthy Chinese volunteers. Ann Phar PubMed
- Ozgoli, G., Selselei, E. A., Mojab, F., and Majd, H. A. A randomized, placebo-controlled trial of Ginkgo biloba L. in treatment of premenstrual syndrome. J Altern.Complement Med 2009;15(8):845-851.
- Singh, V., Singh, S. P., and Chan, K. Review and meta-analysis of usage of ginkgo as an adjunct therapy in chronic schizophrenia. Int J Neuropsychopharmacol. 2010;13(2):257-271.
- Kim, T. E., Kim, B. H., Kim, J., Kim, K. P., Yi, S., Shin, H. S., Lee, Y. O., Lee, K. H., Shin, S. G., Jang, I. J., and Yu, K. S. Comparison of the pharmacokinetics of ticlopidine between administration of a combined fixed-dose tablet formulation of ticl
- Nicolai, S. P., Gerardu, V. C., Kruidenier, L. M., Prins, M. H., and Teijink, J. A. From the Cochrane library: Ginkgo biloba for intermittent claudication. Vasa 2010;39(2):153-158. PubMed
- Patel, N. Herbal remedies. Br.Dent.J 8-28-2010;209(4):153.
- Pedroso, J. L., Henriques Aquino, C. C., Escorcio Bezerra, M. L., Baiense, R. F., Suarez, M. M., Dutra, L. A., Braga-Neto, P., and Povoas Barsottini, O. G. Ginkgo biloba and cerebral bleeding: a case report and critical review. Neurologist. 2011;17(2):89 PubMed
- Russo, V., Rago, A., Russo, G. M., Calabro, R., and Nigro, G. Ginkgo biloba: an ancient tree with new arrhythmic side effects. J Postgrad.Med 2011;57(3):221.
- Zhou, Y. and Zeng, R. [Effects of Ginkgo biloba extract on anticoagulation and blood drug level of warfarin in healthy wolunteers]. Zhongguo Zhong Yao Za Zhi 2011;36(16):2290-2293. DOI
- Skogh, M. Extracts of Ginkgo biloba and bleeding or haemorrhage. Lancet 10-3-1998;352(9134):1145-1146. PubMed
- Fessenden JM, Wittenborn W, and Clarke L. Ginkgo biloba: a case report of herbal medicine and bleeding postoperatively from a laparoscopic cholecystectomy. Am Surg 2001;67(1):33-35.
- Burkard G. [The efficacy and safety of ginkgo biloba extract in dementia]. Fortschr Med [Supp] 1991;109(107):6-8.
- Dai LL, Fan L, Wu HZ, Tan ZR, Chen Y, Peng XD, Shen MX, Yang GP, Zhou HH. Assessment of a pharmacokinetic and pharmacodynamic interaction between simvastatin and Ginkgo biloba extracts in healthy subjects. Xenobiotica 2013;43(10):862-7.
- Guo CX, Pei Q, Yin JY, Peng XD, Zhou BT, Zhao YC, Wu LX, Meng XG, Wang G, Li Q, Ouyang DS, Liu ZQ, Zhang W, Zhou HH. Effects of Ginkgo biloba extracts on pharmacokinetics and efficacy of atorvastatin based on plasma indices. Xenobiotica 2012;42(8):784-90.
- Stoddard GJ, Archer M, Shane-McWhorter L, Bray BE, Redd DF, Proulx J, Zeng-Treitler Q. Ginkgo and Warfarin Interaction in a Large Veterans Administration Population. AMIA Annu Symp Proc. 2015 Nov 5;2015:1174-83.
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Carlile PV. Unexplained alveolar hemorrhage associated with ginkgo and ginseng use. J Bronchology Interv Pulmonol. 2015;22(2):170-2. doi: 10.1097/LBR.0000000000000150. PubMed
- Han EJ, Park HL, Kim SH. Allergic Reaction to Ginkgo Nut on FDG PET/CT. Clin Nucl Med. 2016 Sep;41(9):716-7. doi: 10.1097/RLU.0000000000001276. PubMed
- Rho SS, Woo YS, Bahk WM. Ginkgo biloba induced mood dysregulation: a case report. BMC Complement Altern Med. 2018 Jan 15;18(1):14. PubMed
- Aziz TA, Hussain SA, Mahwi TO, Ahmed ZA, Rahman HS, Rasedee A. The efficacy and safety of Ginkgo biloba extract as an adjuvant in type 2 diabetes mellitus patients ineffectively managed with metformin: a double-blind, randomized, placebo-controlled trial.
- World Health Organization. WHO pharmaceuticals newsletter: 2020, No. 3. Available at: https://www.who.int/medicines/publications/WHO_Pharmaceuticals_Newslet3_20.pdf?ua=1. Accessed June 23, 2021.
- Health Canada. Ginkgo biloba-containing products and the risk of cardiac arrhythmias. Health Product InfoWatch. February 2021. Available at: https://www.canada.ca/en/health-canada/services/drugs-health-products/medeffect-canada/health-product-infowatch/fe
- Wasef AK, Wahdan SA, Saeed NM, El-Demerdash E. Effects of aged garlic and ginkgo biloba extracts on the pharmacokinetics of sofosbuvir in rats. Biopharm Drug Dispos. 2022;43(4):152-62. PubMed
- Xing X, Kong M, Hou Q, Li J, Qian W, Chen X, Li H, Yang C. Effects of ginkgo leaf tablet on the pharmacokinetics of rosiglitazone in rats and its potential mechanism. Pharm Biol. 2022;60(1):1190-7. PubMed
- Hoerr R, Zimmermann A, Seitz F, Dienel A. Single and repeated doses of EGb 761® do not affect pharmacokinetics or pharmacodynamics of rivaroxaban in healthy subjects. Front Pharmacol. 2022 Apr 20;13:868843. PubMed
- Bai J, Zhang C. Metabolic interaction between biflavonoids in Ginkgo biloba leaves and tacrolimus. Biopharm Drug Dispos 2023;44(2):157-164.
- Wang Q, Liu Z, Wang R, et al. Effect of Ginkgo biloba extract on pharmacology and pharmacokinetics of atorvastatin in rats with hyperlipidaemia. Food Funct 2023;14(7):3051-3066.
- Burnett CL, Bergfeld WF, Belsito DV, et al. Safety Assessment of Ginkgo biloba-Derived Ingredients as Used in Cosmetics. Int J Toxicol. 2023 Nov 6:10915818231210792.
- Yao Y, Zhao J, Li C, et al. Ginkgo biloba extract safety: Insights from a real-world pharmacovigilance study of FDA adverse event reporting system (FAERS) events. J Ethnopharmacol 2025;337(Pt 3):119010. PubMed
Magnesium 82 references
- Rodin SM, Johnson BF. Pharmacokinetic interactions with digoxin. Clin Pharmacokinet 1988;15:227-44.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Dahle LO, Berg G, Hammar M, et al. The effect of oral magnesium substitution on pregnancy-induced leg cramps. Am J Obstet Gynecol 1995;173:175-80. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Peikert A, Wilimzig C, Kohne-Volland R. Prophylaxis of migraine with oral magnesium: results from a prospective, multi-center, placebo-controlled and double-blind randomized study. Cephalalgia 1996;16:257-63. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Washington, DC: National Academy Press, 1999. Available at: http://books.nap.edu/books/0309063507/html/index.html.
- Birrer RB, Shallash AJ, Totten V. Hypermagnesemia-induced fatality following epsom salt gargles. J Emerg Med 2002;22:185-8. PubMed
- Ryan MP. Diuretics and potassium/magnesium depletion. Directions for treatment. Am J Med 1987;82:38-47.. PubMed
- Hollifield JW. Magnesium depletion, diuretics, and arrhythmias. Am J Med 1987;82:30-7.. PubMed
- Heidenreich O. Mode of action of conventional and potassium-sparing diuretics--aspects with relevance to Mg-sparing effects. Magnesium 1984;3:248-56..
- Pfaffenrath V, Wessely P, Meyer C, et al. Magnesium in the prophylaxis of migraine--a double-blind placebo-controlled study. Cephalalgia 1996;16:436-40.. PubMed
- Wang F, Van Den Eeden SK, Ackerson LM, et al. Oral magnesium oxide prophylaxis of frequent migrainous headache in children: a randomized, double-blind, placebo-controlled trial. Headache 2003;43:601-10.. PubMed
- Sompolinsky D, Samra Z. Influence of magnesium and manganese on some biological and physical properties of tetracycline. J Bacteriol 1972;110:468-76.. PubMed
- Jeyabalan A, Caritis SN. Pharmacologic inhibition of preterm labor. Clin Obstet Gynecol 2002;45:99-113. PubMed
- Mittendorf R, Dambrosia J, Pryde PG, et al. Association between the use of antenatal magnesium sulfate in preterm labor and adverse health outcomes in infants. Am J Obstet Gynecol 2002;186:1111-8.. PubMed
- Witlin AG, Sibai BM. Magnesium sulfate therapy in preeclampsia and eclampsia. Obstet Gynecol 1998;92:883-9.. DOI
- Crowther CA, Hiller JE, Doyle LW. Magnesium sulphate for preventing preterm birth in threatened preterm labour. Cochrane Database Syst Rev 2002;4:CD001060. . PubMed
- Davey MJ, Teubner D. A randomized controlled trial of magnesium sulfate, in addition to usual care, for rate control in atrial fibrillation. Ann Emerg Med 2005;45:347-53.. PubMed
- L'Hommedieu CS, Nicholas D, Armes DA, et al. Potentiation of magnesium sulfate--induced neuromuscular weakness by gentamicin, tobramycin, and amikacin. J Pediatr 1983;102:629-31..
- Dunn CJ, Goa KL. Risedronate: a review of its pharmacological properties and clinical use in resorptive bone disease. Drugs 2001;61:685-712..
- Kass L, Weekes J, Carpenter L. Effect of magnesium supplementation on blood pressure: a meta-analysis. Eur J Clin Nutr 2012;66:411-8. PubMed
- Koontz SL, Friedman SA, Schwartz ML. Symptomatic hypocalcemia after tocolytic therapy with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 2004;190(6):1773-6. PubMed
- Snyder SW, Cardwell MS. Neuromuscular blockade with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 1989;161(1):35-6. PubMed
- Waisman GD, Mayorga LM, Cámera MI, et al. Magnesium plus nifedipine: potentiation of hypotensive effect in preeclampsia? Am J Obstet Gynecol. 1988;159(2):308-9. PubMed
- Brown DD, Juhl RP. Decreased bioavailability of digoxin due to antacids and kaolin-pectin. N Engl J Med. 1976;295(19):1034-7. PubMed
- Allen MD, Greenblatt DJ, Harmatz JS, et al. Effect of magnesium--aluminum hydroxide and kaolin--pectin on absorption of digoxin from tablets and capsules. J Clin Pharmacol. 1981;21(1):26-30. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an in vitro study. Thromb Haemost. 1996;76(1):88-93. DOI
- Ravn HB, Kristensen SD, Vissinger H, et al. Magnesium inhibits human platelets. Blood Coagul Fibrinolysis. 1996;7(2):241-4. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an infusion study in healthy volunteers. Thromb Haemost. 1996;75(6):939-44. DOI
- Neuvonen PJ, Kivistö KT. The effects of magnesium hydroxide on the absorption and efficacy of two glibenclamide preparations. Br J Clin Pharmacol. 1991;32(2):215-20. PubMed
- Kivistö KT, Neuvonen PJ. Enhancement of absorption and effect of glipizide by magnesium hydroxide. Clin Pharmacol Ther. 1991;49(1):39-43. PubMed
- Neuvonen PJ, Kivistö KT. Enhancement of drug absorption by antacids. An unrecognised drug interaction. Clin Pharmacokinet. 1994;27(2):120-8. PubMed
- Shechter, M., Merz, C. N., Paul-Labrador, M., Meisel, S. R., Rude, R. K., Molloy, M. D., Dwyer, J. H., Shah, P. K., and Kaul, S. Beneficial antithrombotic effects of the association of pharmacological oral magnesium therapy with aspirin in coronary heart
- Ganzevoort, J. W., Hoogerwaard, E. M., and van der Post, J. A. [Hypocalcemic delirium due to magnesium sulphate therapy in a pregnant woman with pre-eclampsia]. Ned.Tijdschr.Geneeskd. 8-3-2002;146(31):1453-1456.
- Horner, S. M. Efficacy of intravenous magnesium in acute myocardial infarction in reducing arrhythmias and mortality. Meta-analysis of magnesium in acute myocardial infarction. Circulation 1992;86(3):774-779. PubMed
- Azria, E., Tsatsaris, V., Goffinet, F., Kayem, G., Mignon, A., and Cabrol, D. [Magnesium sulfate in obstetrics: current data]. J Gynecol.Obstet.Biol.Reprod.(Paris) 2004;33(6 Pt 1):510-517.
- Magee, L. A., Miremadi, S., Li, J., Cheng, C., Ensom, M. H., Carleton, B., Cote, A. M., and von Dadelszen, P. Therapy with both magnesium sulfate and nifedipine does not increase the risk of serious magnesium-related maternal side effects in women with p
- Henyan, N. N., Gillespie, E. L., White, C. M., Kluger, J., and Coleman, C. I. Impact of intravenous magnesium on post-cardiothoracic surgery atrial fibrillation and length of hospital stay: a meta-analysis. Ann.Thorac.Surg. 2005;80(6):2402-2406. PubMed
- Li, J., Zhang, Q., Zhang, M., and Egger, M. Intravenous magnesium for acute myocardial infarction. Cochrane.Database.Syst.Rev. 2007;(2):CD002755. PubMed
- Doyle, L. W., Crowther, C. A., Middleton, P., Marret, S., and Rouse, D. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane.Database.Syst.Rev. 2009;(1):CD004661. PubMed
- Han, S., Crowther, C. A., and Moore, V. Magnesium maintenance therapy for preventing preterm birth after threatened preterm labour. Cochrane.Database.Syst.Rev. 2010;(7):CD000940. PubMed
- Duley, L., Gulmezoglu, A. M., Henderson-Smart, D. J., and Chou, D. Magnesium sulphate and other anticonvulsants for women with pre-eclampsia. Cochrane.Database.Syst.Rev. 2010;(11):CD000025. PubMed
- Conde-Agudelo, A., Romero, R., and Kusanovic, J. P. Nifedipine in the management of preterm labor: a systematic review and metaanalysis. Am J Obstet.Gynecol. 2011;204(2):134-20. PubMed
- Wong, G. K., Boet, R., Poon, W. S., Chan, M. T., Gin, T., Ng, S. C., and Zee, B. C. Intravenous magnesium sulphate for aneurysmal subarachnoid hemorrhage: an updated systemic review and meta-analysis. Crit Care 2011;15(1):R52. PubMed
- Magee, L., Sawchuck, D., Synnes, A., and von, Dadelszen P. SOGC Clinical Practice Guideline. Magnesium sulphate for fetal neuroprotection. J Obstet.Gynaecol.Can. 2011;33(5):516-529.
- Doyle, L. W. Antenatal magnesium sulfate and neuroprotection. Curr Opin Pediatr 2012;24(2):154-159. PubMed
- McDonald, S. D., Lutsiv, O., Dzaja, N., and Duley, L. A systematic review of maternal and infant outcomes following magnesium sulfate for pre-eclampsia/eclampsia in real-world use. Int J Gynaecol.Obstet. 2012;118(2):90-96. PubMed
- Gordon, M., Naidoo, K., Akobeng, A. K., and Thomas, A. G. Osmotic and stimulant laxatives for the management of childhood constipation. Cochrane.Database.Syst.Rev. 2012;7:CD009118. PubMed
- Dodd, J. M., Crowther, C. A., and Middleton, P. Oral betamimetics for maintenance therapy after threatened preterm labour. Cochrane.Database.Syst.Rev. 2012;12:CD003927. PubMed
- Wu, X., Wang, C., Zhu, J., Zhang, C., Zhang, Y., and Gao, Y. Meta-analysis of randomized controlled trials on magnesium in addition to beta-blocker for prevention of postoperative atrial arrhythmias after coronary artery bypass grafting. BMC.Cardiovasc.D PubMed
- Thorp, J. M., Jr., Katz, V. L., Campbell, D., and Cefalo, R. C. Hypersensitivity to magnesium sulfate. Am.J.Obstet.Gynecol. 1989;161(4):889-890. PubMed
- Duley L and Gulmezoglu AM. Magnesium sulphate versus lytic cocktail for eclampsia. Cochrane Database of Systematic Reviews 2000;(3) PubMed
- Gibbins KJ, Browning KR, Lopes VV, Anderson BL, Rouse DJ. Evaluation of the clinical use of magnesium sulfate for cerebral palsy prevention. Obstet Gynecol 2013;121(2 Pt 1):235-40. PubMed
- Ji D. Oral magnesium sulfate causes perforation during bowel preparation for fiberoptic colonoscopy in patients with colorectal cancer. J Emerg Med 2012;43(4):716-7. PubMed
- Yagi T, Naito T, Mino Y, Umemura K, Kawakami J. Impact of concomitant antacid administration on gabapentin plasma exposure and oral bioavailability in healthy adult subjects. Drug Metab Pharmacokinet 2012;27(2):248-54. PubMed
- Yamasaki M, Funakoshi S, Matsuda S, Imazu T, Takeda Y, Murakami T, Maeda Y. Interaction of magnesium oxide with gastric acid secretion inhibitors in clinical pharmacotherapy. Eur J Clin Pharmacol 2014;70(8):921-4. PubMed
- Choi ES, Jeong WJ, Ahn SH, Oh AY, Jeon YT, Do SH. Magnesium sulfate accelerates the onset of low-dose rocuronium in patients undergoing laryngeal microsurgery. J Clin Anesth. 2017 Feb;36:102-106. PubMed
- Ikee R, Toyoyama T, Endo T, Tsunoda M, Hashimoto N. Impact of sevelamer hydrochloride on serum magnesium concentrations in hemodialysis patients. Magnes Res. 2016 Apr 1;29(4):184-90. PubMed
- Miller ES, Sakowicz A, Leger E. Lange E, Yee LM. The association between receipt of intrapartum magnesium and postpartum hemorrhage. Am J Obstet Gynecol 2018;218(1 Suppl):S165.
- Rodríguez-Rubio L, Solis Garcia Del Pozo J, Nava E, Jordán J. Interaction between magnesium sulfate and neuromuscular blockers during the perioperative period. A systematic review and meta-analysis. J Clin Anesth. 2016;34:524-34. PubMed
- Brown RS. Magnesium Sulfate: Another Cause of a Solute Diuresis. Am J Kidney Dis. 2017;69(4):550-551. PubMed
- Park H, Qin R, Smith TJ, et al. North Central Cancer Treatment Group N10C2 (Alliance): a double-blind placebo-controlled study of magnesium supplements to reduce menopausal hot flashes. Menopause. 2015;22(6):627-32. PubMed
- Sakanoue M, Sanada J, Kanekura T. Skin eruption elicited by magnesium oxide (Maglax). J Dermatol. 2016;43(2):221-2.
- Iwamuro M, Saito S, Yoshioka M, et al. A Magnesium Oxide Bezoar. Intern Med. 2018;57(21):3087-3091. PubMed
- Vilchez G, Dai J, Kumar K, Mundy D, Kontopoulos E, Sokol RJ. Racial/ethnic disparities in magnesium sulfate neuroprotection: a subgroup analysis of a multicenter randomized controlled trial. J Matern Fetal Neonatal Med. 2018;31(17):2304-2311. PubMed
- Drug Safety Communication: FDA Recommends Against Prolonged Use of Magnesium Sulfate to Stop Pre-term Labor Due to Bone Changes in Exposed Babies. U.S. Food and Drug Administration (FDA), May 30, 2013. https://www.fda.gov/downloads/Drugs/DrugSafety/UCM353
- Committee Opinion: Magnesium Sulfate Use in Obstetrics. The American College of Obstetricians and Gynecologists Committee on Obstetric Practice Society for Maternal-Fetal Medicine, Number 652, January 2016. https://www.acog.org/Clinical-Guidance-and-Publi
- Kashihara Y, Terao Y, Yoda K, et al. Effects of magnesium oxide on pharmacokinetics of L-dopa/carbidopa and assessment of pharmacodynamic changes by a model-based simulation. Eur J Clin Pharmacol. 2019;75(3):351-361. PubMed
- Shepherd E, Salam RA, Manhas D, et al. Antenatal magnesium sulphate and adverse neonatal outcomes: A systematic review and meta-analysis. PLoS Med. 2019;16(12):e1002988. PubMed
- Hong JY, Hong JY, Choi YS, et al. Antenatal magnesium sulfate treatment and risk of necrotizing enterocolitis in preterm infants born at less than 32 weeks of gestation. Sci Rep. 2020;10(1):12826. PubMed
- Schuh S, Sweeney J, Rumantir M, et al. Effect of nebulized magnesium vs placebo added to albuterol on hospitalization among children with refractory acute asthma treated in the emergency department: a randomized clinical trial. JAMA. 2020;324(20):2038-20 PubMed
- Almeida CED, Carvalho LR, Andrade CVC, Nascimento PD Jr, Barros GAM, Modolo NSP. Effects of magnesium sulphate on the onset time of rocuronium at different doses: a randomized clinical trial. Braz J Anesthesiol. 2021;71(5):482-8. PubMed
- Gochi Valdovinos A, Arriaga-Redondo M, Dejuan Bitriá E, Pérez Rodríguez I, Márquez Isidro E, Blanco Bravo D. Prenatal therapy with magnesium sulphate and intestinal obstruction due to meconium in preterm newborns. An Pediatr (Engl Ed). 2022 Feb;96(2):138- PubMed
- Iio K, Kondo E, Shibata E, et al. Long-term tocolysis with magnesium sulfate as a risk factor for low bone mass: a case series. J Med Cases. 2022 Feb;13(2):47-50. PubMed
- Eiraku K, Uozumi Y, Hieda M, Maruyama T, Nomura H. A senile case of heart failure associated with hypermagnesemia induced by magnesium-containing laxative agent. Geriatr Gerontol Int. 2022;22(10):897-899.
- Enayati A, Gin JH, Sajeev JK, et al. Efficacy of intravenous magnesium for the management of non-post operative atrial fibrillation with rapid ventricular response: A systematic review and meta-analysis. J Cardiovasc Electrophysiol 2023;34(5):1286-1295. PubMed
- Su YH, Luo DC, Pang Y. Effects of intraoperative Magnesium sulfate infusion on emergency agitation during general anesthesia in patients undergoing radical mastectomy: a randomized controlled study. BMC Anesthesiol 2023;23(1):326. PubMed
- Han J, Park HY, Shin HJ, Chung SH, Do SH. Effects of magnesium sulphate on neostigmine-induced recovery from moderate neuromuscular blockade with rocuronium: a randomized controlled trial. Magnes Res 2023;36(2):31-39. PubMed
- Lee AT, Cordova JC, Jamplis RP, Pomicter GR. Posterior Reversible Encephalopathy Syndrome and Eclampsia in the Setting of Magnesium Toxicity: A Case Report. A A Pract 2023;17(11):e01726. PubMed
- Darmawan D, Rengganis I, Rumende CM, et al. Effectiveness and Safety of Nebulized Magnesium as Last Line Treatment in Adults with Acute Asthma Attack: A Systematic Review and Meta-Analysis. Acta Med Indones 2024;56(1):3-12.
- Shepherd ES, Goldsmith S, Doyle LW, et al. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane Database Syst Rev 2024;5(5):CD004661. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Quercetin 26 references
- Shoskes DA, Zeitlin SI, Shahed A, Rajfer J. Quercetin in men with category III chronic prostatitis: A preliminary prospective, double-blind, placebo-controlled trial. Urol 1999;54:960-3. PubMed
- Starvic B. Quercetin in our diet: from potent mutagen to probable anticarcinogen. Clin Biochem 1994;27:245-8. PubMed
- Ferry DR, Smith A, Malkhandi J, et al. Phase I clinical trial of the flavonoid quercetin: Pharmacokinetics and evidence for in vivo tyrosine kinase inhibition. Clin Cancer Res 1996;2:659-67..
- Obach RS. Inhibition of human cytochrome P450 enzymes by constituents of St. John's wort, an herbal preparation used in the treatment of depression. J Pharmacol Exp Ther 2000;294:88-95. DOI
- Edwards RL, Lyon T, Litwin SE, et al. Quercetin reduces blood pressure in hypertensive subjects. J Nutr 2007;137:2405-11.
- Kim KA, Park PW, Kim HK, et al. Effect of quercetin on the pharmacokinetics of rosiglitazone, a CYP2C8 substrate, in healthy subjects. J Clin Pharmacol 2005;45:941-6. PubMed
- DiCenzo R, Frerichs V, Larppanichpoonphol P, et al. Effect of quercetin on the plasma and intracellular concentrations of saquinavir in healthy adults. Pharmacotherapy 2006;26:1255-61. PubMed
- Choi JS, Choi BC, Choi KE. Effect of quercetin on the pharmacokinetics of oral cyclosporine. Am J Health Syst Pharm 2004;61:2406-9. PubMed
- Choi JS, Jo BW, Kim YC. Enhanced paclitaxel bioavailability after oral administration of paclitaxel or prodrug to rats pretreated with quercetin. Eur J Pharm Biopharm 2004;57:313-8. PubMed
- Vaclavikova R, Horsky S, Simek P, Gut I. Paclitaxel metabolism in rat and human liver microsomes is inhibited by phenolic antioxidants. Naunyn Schmiedebergs Arch Pharmacol 2003;368:200-9. PubMed
- Di Bari L, Ripoli S, Pradhan S, Salvadori P. Interactions between quercetin and warfarin for albumin binding: A new eye on food/drug interference. Chirality 2010;22:593-6. PubMed
- Lamson, D. W. and Brignall, M. S. Antioxidants and cancer, part 3: quercetin. Altern.Med.Rev. 2000;5(3):196-208.
- Duan KM, Wang SY, Ouyang W, Mao YM, Yang LJ. Effect of quercetin on CYP3A activity in Chinese healthy participants. J Clin Pharmacol 2012;52(6):940-6. PubMed
- Wang SY, Duan KM, Li Y, et al. Effect of quercetin on P-glycoprotein transport ability in Chinese healthy subjects. Eur J Clin Nutr 2013;67(4):390-4. PubMed
- Nguyen MA, Staubach P, Wolffram S, Langguth P. Effect of single-dose and short-term administration of quercetin on the pharmacokinetics of talinolol in humans - Implications for the evaluation of transporter-mediated flavonoid-drug interactions. Eur J Pha PubMed
- Wu LX, Guo CX, Chen WQ, et al. Inhibition of the organic anion-transporting polypeptide 1B1 by quercetin: an in vitro and in vivo assessment. Br J Clin Pharmacol 2012;73(5):750-7.
- Ahrens MJ, Thompson DL. Effect of emulin on blood glucose in type 2 diabetics. J Med Food. 2013;16(3):211-5. PubMed
- Larson A, Witman MA, Guo Y, et al. Acute, quercetin-induced reductions in blood pressure in hypertensive individuals are not secondary to lower plasma angiotensin-converting enzyme activity or endothelin-1: nitric oxide. Nutr Res. 2012;32(8):557-64. PubMed
- Bedada SK, Neerati P. Evaluation of the effect of quercetin treatment on CYP2C9 enzyme activity of diclofenac in healthy human volunteers. Phytother Res. 2018 Feb;32(2):305-311. doi: 10.1002/ptr.5978. PubMed
- Zhao Q, Wei J, Zhang H. Effects of quercetin on the pharmacokinetics of losartan and its metabolite EXP3174 in rats. Xenobiotica 2019;49(5):563-8. PubMed
- Bhutani P, Rajanna PK, Paul AT. Impact of quercetin on pharmacokinetics of quetiapine: insights from in-vivo studies in wistar rats. Xenobiotica. 2020:1-7.
- Li C, Wang X, Bi Y, et al. Potent Inhibitors of Organic Anion Transporters 1 and 3 From Natural Compounds and Their Protective Effect on Aristolochic Acid Nephropathy. Toxicol Sci. 2020;175(2):279-291. PubMed
- Ni Y, Duan Z, Zhou D, et al. Identification of Structural Features for the Inhibition of OAT3-Mediated Uptake of Enalaprilat by Selected Drugs and Flavonoids. Front Pharmacol. 2020;11:802. PubMed
- Song YK, Yoon JH, Woo JK, et al. Quercetin is a flavonoid breast cancer resistance protein inhibitor with an impact on the oral pharmacokinetics of sulfasalazine in rats. Pharmaceutics 2020;12(5):397. PubMed
- Ahmad E, Jahangir M, Ismail MA, et al. Influence of quercetin pretreatment on pharmacokinetics of warfarin in rats. Curr Drug Saf 2022. PubMed
- Nambiar A, Kellogg D 3rd, Justice J, et al. Senolytics dasatinib and quercetin in idiopathic pulmonary fibrosis: results of a phase I, single-blind, single-center, randomized, placebo-controlled pilot trial on feasibility and tolerability. EBioMedicine 20 PubMed
Vitamin A 31 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Griffiths JK. The vitamin A paradox. J Pediatr 2000;137:604-7.. PubMed
- Hardman JG, Limbird LL, Molinoff PB, eds. Goodman and Gillman's The Pharmacological Basis of Therapeutics, 9th ed. New York, NY: McGraw-Hill, 1996.
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- FDA Talk Paper. Vitamin A and birth defects (T95-56). Food and Drug Administration, U.S. Department of Health and Human Services, Rockville, MD. October 6, 1995.
- Russell RM. The vitamin A spectrum: from deficiency to toxicity. Am J Clin Nutr 2000;71:878-84. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Feskanich D, Singh V, Willett WC, Colditz GA. Vitamin A intake and hip fractures among postmenopausal women. JAMA 2002;287:47-54. PubMed
- Melhus H, Michaelsson K, Kindmark A, et al. Excessive dietary intake of vitamin A is associated with reduced bone mineral density and increased risk for hip fracture. Ann Intern Med 1998;129:770-8. PubMed
- Michaelsson K, Lithell H, Vessby B, Melhus H. Serum retinol levels and the risk of fracture. N Engl J Med 2003;348:287-94.. PubMed
- Botterweck AA, van den Brandt PA, Goldbohm RA. Vitamins, carotenoids, dietary fiber, and the risk of gastric carcinoma: results from a prospective study after 6.3 years of follow-up. Cancer 2000;88:737-48.. DOI
- Meyskens FL Jr, Graham V, Chvapil M, et al. A phase I trial of beta-all-trans-retinoic acid delivered via a collagen sponge and a cervical cap for mild or moderate intraepithelial cervical neoplasia. J Natl Cancer Inst 1983;71:921-5..
- Hathcock JN, Hattan DG, Jenkins MY, et al. Evaluation of vitamin A toxicity. Am J Clin Nutr 1990;52:183-202.. PubMed
- Walters BN, Gubbay SS. Tetracycline and benign intracranial hypertension: report of five cases. Br Med J 1981;282:19-20.. PubMed
- Pearson MG, Littlewood SM, Bowden AN. Tetracycline and benign intracranial hypertension (letter). Br Med J 1981;282:568-9.. PubMed
- Azais-Braesco V, Pascal G. Vitamin A in pregnancy: requirements and safety limits. Am J Clin Nutr 2000;71:1325S-33S. PubMed
- Smedts HP, de Vries JH, Rakhshandehroo M, et al. High maternal vitamin E intake by diet or supplements is associated with congenital heart defects in the offspring. BJOG 2009;116:416-23. PubMed
- Grotto, I., Mimouni, M., Gdalevich, M., and Mimouni, D. Vitamin A supplementation and childhood morbidity from diarrhea and respiratory infections: a meta-analysis. J Pediatr 2003;142(3):297-304. PubMed
- Mahalanabis, D., Lahiri, M., Paul, D., Gupta, S., Gupta, A., Wahed, M. A., and Khaled, M. A. Randomized, double-blind, placebo-controlled clinical trial of the efficacy of treatment with zinc or vitamin A in infants and young children with severe acute l
- Long, K. Z., Montoya, Y., Hertzmark, E., Santos, J. I., and Rosado, J. L. A double-blind, randomized, clinical trial of the effect of vitamin A and zinc supplementation on diarrheal disease and respiratory tract infections in children in Mexico City, Mex
- Fritz, H., Kennedy, D., Fergusson, D., Fernandes, R., Doucette, S., Cooley, K., Seely, A., Sagar, S., Wong, R., and Seely, D. Vitamin A and retinoid derivatives for lung cancer: a systematic review and meta analysis. PLoS.One. 2011;6(6):e21107. PubMed
- Mayo-Wilson, E., Imdad, A., Herzer, K., Yakoob, M. Y., and Bhutta, Z. A. Vitamin A supplements for preventing mortality, illness, and blindness in children aged under 5: systematic review and meta-analysis. BMJ 2011;343:d5094. PubMed
- Mazumder S, Taneja S, Bhatia K, Yoshida S, Kaur J, Dube B, Toteja GS, Bahl R, Fontaine O, Martines J, Bhandari N; Neovita India Study Group. Efficacy of early neonatal supplementation with vitamin A to reduce mortality in infancy in Haryana, India (Neovit
- Baineni R, Gulati R, Delhi CK. Vitamin A toxicity presenting as bone pain. Arch Dis Child. 2017;102(6):556-8. PubMed
- Darlow BA, Graham PJ, Rojas-Reyes MX. Vitamin A supplementation to prevent mortality and short- and long-term morbidity in very low birth weight infants. Cochrane Database Syst Rev. 2016;(8):CD000501. PubMed
- Haider BA, Sharma R, Bhutta ZA. Neonatal vitamin A supplementation for the prevention of mortality and morbidity in term neonates in low and middle income countries. Cochrane Database Syst Rev. 2017;2:CD006980. PubMed
- Mohammad YM, Raslan IR, Al-Hussain FA. Idiopathic Intracranial Hypertension Induced by Topical Application of Vitamin A. J Neuroophthalmol. 2016;36(4):412-3. PubMed
- Masnadi Shirazi K, Nikniaz Z, Masnadi Shirazi A, Rohani M. Vitamin A supplementation decreases disease activity index in patients with ulcerative colitis: A randomized controlled clinical trial. Complement Ther Med. 2018 Dec;41:215-219. PubMed
- Ding Y, Hu P, Yang Y, et al. Impact of maternal daily oral low-dose vitamin A supplementation on the mother-infant pair: a randomised placebo-controlled trial in China. Nutrients 2021;13(7):2370. PubMed
- Knapik JJ, Hoedebecke SS. Vitamin A and bone fractures: systematic review and meta-analysis. J Spec Oper Med 2021;21(2):100-7. PubMed
- Imdad A, Mayo-Wilson E, Haykal MR, et al. Vitamin A supplementation for preventing morbidity and mortality in children from six months to five years of age. Cochrane Database Syst Rev 2022;3(3):CD008524. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC