
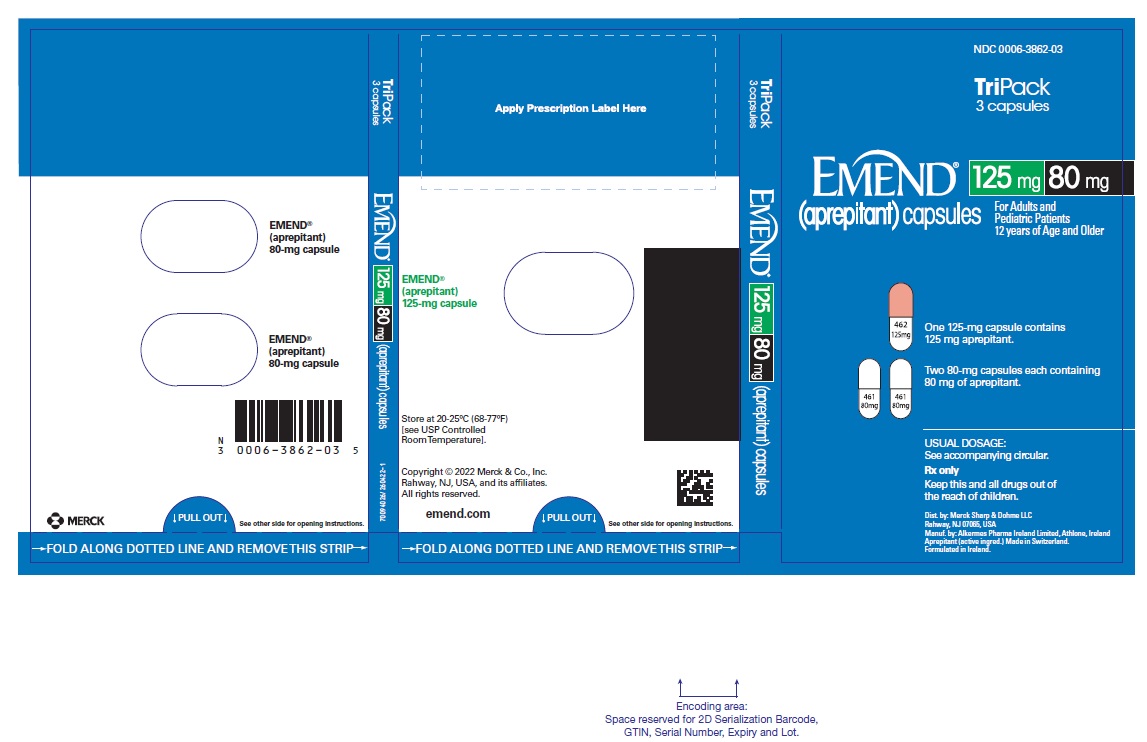
EMEND aprepitant Kit
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Substance P/Neurokinin-1 Receptor Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Aprepitant is used with other medications in adults and children 6 months of age and older to prevent nausea and vomiting that may occur after receiving cancer chemotherapy treatment. It is also used with other medications in adults and children 6 months of age and older to prevent delayed nausea and vomiting that may occur several days after receiving certain chemotherapy medications. Aprepitant is not used to treat nausea and vomiting that you already have. Aprepitant is in a class of medications called antiemetics. It works by blocking the action of neurokinin, a natural substance in the br...
Read the full MedlinePlus article ↗- Aprepitant is designed to prevent nausea and vomiting before they start — not to treat them once they've kicked in. It's given as part of a combination of anti-nausea medicines, us...
- What exactly is this medicine supposed to do for me?
- Not without a backup plan. Aprepitant can reduce how well hormonal birth control works — that includes the pill, the patch, implants, and some IUDs. This effect can last for a full...
- Can I take my birth control as usual while I'm on this?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Aprepitant — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $356.69 | — |
| Medicare Part B allowsASP · J8501 | $3.069 / J8501 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Aprepitant 13668-0594-87 | Torrent | 1 capsule | $87.266 | AB | Availability likely | — |
| Aprepitant 68462-0112-33 | Glenmark | 1 kit | $87.266 | AB | Availability likely | — |
| Aprepitant 68001-0669-15 | BluePoint | 1 capsule | $87.266 | AB | Availability likely | — |
| Aprepitant 00781-4063-36 | Sandoz | 1 capsule | $87.266 | AB | Availability likely | — |
| Emendthis 00006-3862-13 | Merck | 1 capsule | — | AB | FDA listed | — |
| Aprepitant 51407-0704-03 | Golden | 1 capsule | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8258132 ↗ | Method of use | U-901 | Sep 26, 2027 |
| US 8258132 ↗ | Method of use | U-1743 | Sep 26, 2027 |
| US 8258132 ↗ | Method of use | U-901 | Sep 26, 2027 |
| US 8258132 ↗ | Method of use | U-1743 | Sep 26, 2027 |
| US 8258132 ↗ | Method of use | U-1743 | Sep 26, 2027 |
| US 8258132 ↗ | Method of use | U-901 | Sep 26, 2027 |
Is there a generic version of EMEND TRIPACK?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00006-3862-03 | 1 KIT in 1 DOSE PACK (0006-3862-03) * 1 CAPSULE in 1 CAPSULE * 1 CAPSULE in 1 CAPSULE | 2003-03-26 | Active |
| 00006-3862-13 You're viewing this | 1 KIT in 1 DOSE PACK (0006-3862-13) * 1 CAPSULE in 1 CAPSULE * 1 CAPSULE in 1 CAPSULE | 2003-03-26 | Active |
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 00006-3862-13?
What NDC number is used to bill for this package of EMEND aprepitant Kit?
🧭 About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE EMEND ® for oral suspension, in combination with other antiemetic agents, is indicated in patients 6 months of age and older for the prevention of: acute and delayed nausea and vomiting associated with initial and repeat courses of highly emetogenic cancer chemotherapy (HEC) including high-dose cisplatin. nausea and vomiting associated with initial and repeat courses of moderately emetogenic cancer chemotherapy (MEC). EMEND ® capsules, in combination with other antiemetic agents, is indicated in patients 12 years of age and older for the prevention of: acute and delayed nausea and vomiting associated with initial and repeat courses of highly emetogenic cancer chemotherapy (HEC) including high-dose cisplatin. nausea and vomiting associated with initial and repeat courses of moderately emetogenic cancer chemotherapy (MEC).
EMEND ® is a substance P/neurokinin 1 (NK 1 ) receptor antagonist. EMEND for oral suspension is indicated in combination with other antiemetic agents, in patients 6 months of age and older for prevention of: acute and delayed nausea and vomiting associated with initial and repeat courses of highly emetogenic cancer chemotherapy (HEC) including high-dose cisplatin ( 1 ) nausea and vomiting associated with initial and repeat courses of moderately emetogenic cancer chemotherapy (MEC) ( 1 ) EMEND capsules is indicated in combination with other antiemetic agents, in patients 12 years of age and older for prevention of: acute and delayed nausea and vomiting associated with initial and repeat courses of highly emetogenic cancer chemotherapy (HEC) including high-dose cisplatin ( 1 ) nausea and vomiting associated with initial and repeat courses of moderately emetogenic cancer chemotherapy (MEC) ( 1 ) Limitations of Use ( 1 ) EMEND has not been studied for treatment of established nausea and vomiting.
Chronic continuous administration of EMEND is not recommended. Limitations of Use EMEND has not been studied for the treatment of established nausea and vomiting. Chronic continuous administration of EMEND is not recommended because it has not been studied, and because the drug interaction profile may change during chronic continuous use.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended Dosage ( 2.1 ) EMEND capsules in adults and pediatric patients 12 years of age and older: is 125 mg on Day 1 and 80 mg on Days 2 and 3. EMEND for oral suspension in pediatric patients 6 months to less than 12 years of age or pediatric and adult patients unable to swallow capsules: see dosing recommendations in Table 3 in the Full Prescribing Information. Administer EMEND 1 hour prior to chemotherapy on Days 1, 2, and 3.
If no chemotherapy is given on Days 2 and 3, administer EMEND in morning. See Full Prescribing Information for recommended dosages of concomitant dexamethasone and 5-HT 3 antagonist for HEC and MEC. Preparation and Administration ( 2.2 , 2.3 ) EMEND capsules and EMEND for oral suspension can be administered with or without food.
Swallow EMEND capsules whole. EMEND for oral suspension should be prepared by healthcare provider. Once prepared, it may be administered either by a healthcare provider, patient, or caregiver.
For details on preparation see Full Prescribing Information.
2.1Recommended Dosage Adults and Pediatric Patients 12 Years of Age and Older The recommended oral dosage of EMEND capsules, dexamethasone, and a 5-HT 3 antagonist in adults and pediatric patients 12 years of age and older who can swallow oral capsules, for the prevention of nausea and vomiting associated with administration of HEC or MEC is shown in Table 1 or Table 2, respectively. For patients who cannot swallow oral capsules, EMEND for oral suspension can be used instead of EMEND capsules as shown in Table 3. Table 1: Recommended Dosing for the Prevention of Nausea and Vomiting Associated with HEC Population Day 1 Day 2 Day 3 Day 4 EMEND capsules Administer EMEND capsules 1 hour prior to chemotherapy treatment on Days 1, 2, and 3.
If no chemotherapy is given on Days 2 and 3, administer EMEND capsules in the morning. Adults and Pediatric Patients 12 Years and Older 125 mg orally 80 mg orally 80 mg orally none Dexamethasone Adults 12 mg orally 8 mg orally 8 mg orally 8 mg orally Pediatric Patients 12 Years and Older If a corticosteroid, such as dexamethasone, is co-administered, administer 50% of the recommended corticosteroid dose on Days 1 through 4 [see Clinical Studies (14.3) ] . Administer dexamethasone 30 minutes prior to chemotherapy treatment on Day 1 and in the morning on Days 2 through 4.
A 50% dosage reduction of dexamethasone is recommended to account for a drug interaction with EMEND [see Clinical Pharmacology (12.3) ] . 5-HT 3 antagonist Adults and Pediatric Patients 12 Years and Older See selected 5-HT 3 antagonist prescribing information for the recommended dosage none none none Table 2: Recommended Dosing for the Prevention of Nausea and Vomiting Associated with MEC Population Day 1 Day 2 Day 3 EMEND capsules Administer EMEND capsules 1 hour prior to chemotherapy treatment on Days 1, 2, and 3.
If no chemotherapy is given on Days 2 and 3, administer EMEND capsules in the morning. Adults and Pediatric Patients 12 Years and Older 125 mg orally 80 mg orally 80 mg orally Dexamethasone Adults 12 mg orally none none Pediatric Patients 12 Years and Older If a corticosteroid, such as dexamethasone, is co-administered, administer 50% of the recommended corticosteroid dose on Days 1 through 4 [see Clinical Studies (14.3) ] . Administer dexamethasone 30 minutes prior to chemotherapy treatment on Day 1.
A 50% dosage reduction of dexamethasone is recommended to account for a drug interaction with EMEND [see Clinical Pharmacology (12.3) ] . 5-HT 3 antagonist Adults and Pediatric Patients 12 Years and Older See the selected 5-HT 3 antagonist prescribing information for recommended dosage none none Pediatric Patients 6 Months to less than 12 Years of Age or Pediatric and Adult Patients Unable to Swallow Capsules The recommended dose of EMEND for oral suspension to be administered with a 5-HT 3 antagonist, with or without a corticosteroid, for the prevention of nausea and vomiting associated with…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS EMEND capsules: 80 mg and 125 mg ( 3 ) EMEND for oral suspension: 125 mg ( 3 ) EMEND capsules: 80 mg: white body and cap with "461" and "80 mg" printed radially in black ink on the body. 125 mg: white body and pink cap with "462" and "125 mg" printed radially in black ink on the body. EMEND for oral suspension: 125 mg as a pink to light pink powder in a single-use pouch with one 1 mL oral dosing dispenser, one 5 mL oral dosing dispenser, one cap and mixing cup.
⛔ Contraindications ▾
4 CONTRAINDICATIONS EMEND is contraindicated in patients: who are hypersensitive to any component of the product. Hypersensitivity reactions including anaphylactic reactions have been reported [see Adverse Reactions (6.2) ] . taking pimozide. Inhibition of CYP3A4 by aprepitant could result in elevated plasma concentrations of this drug which is a CYP3A4 substrate, potentially causing serious or life-threatening reactions, such as QT prolongation, a known adverse reaction of pimozide [see Warnings and Precautions (5.1) ] .
Known hypersensitivity to any component of this drug. ( 4 ) Concurrent use with pimozide. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS CYP3A4 Interactions : Aprepitant is a substrate, weak-to-moderate inhibitor and inducer of CYP3A4; See Full Prescribing Information for recommendations regarding contraindications, risk of adverse reactions, and dosage adjustments of EMEND and concomitant drugs. ( 4 , 5.1 , 7.1 , 7.2 ) Warfarin (a CYP2C9 substrate) : Risk of decreased INR of prothrombin time; monitor INR in 2-week period, particularly at 7 to 10 days, following initiation of EMEND. ( 5.2 , 7.1 ) Hormonal Contraceptives : Efficacy of contraceptives may be reduced during administration of and for 28 days following the last dose of EMEND.
Use effective alternative or back-up methods of contraception. ( 5.3 , 7.1 , 8.3 )
5.1Clinically Significant CYP3A4 Drug Interactions Aprepitant is a substrate, a weak-to-moderate (dose-dependent) inhibitor, and an inducer of CYP3A4. Use of EMEND with other drugs that are CYP3A4 substrates, may result in increased plasma concentration of the concomitant drug. Use of pimozide with EMEND is contraindicated due to the risk of significantly increased plasma concentrations of pimozide, potentially resulting in prolongation of the QT interval, a known adverse reaction of pimozide [see Contraindications (4) ].
Use of EMEND with strong or moderate CYP3A4 inhibitors (e.g., ketoconazole, diltiazem) may increase plasma concentrations of aprepitant and result in an increased risk of adverse reactions related to EMEND. Use of EMEND with strong CYP3A4 inducers (e.g., rifampin) may result in a reduction in aprepitant plasma concentrations and decreased efficacy of EMEND. See Table 8 and Table 9 for a listing of potentially significant drug interactions [see Drug Interactions (7.1 , 7.2) ].
5.2Decrease in INR with Concomitant Warfarin Coadministration of EMEND with warfarin, a CYP2C9 substrate, may result in a clinically significant decrease in International Normalized Ratio (INR) of prothrombin time [see Clinical Pharmacology (12.3) ] . Monitor the INR in patients on chronic warfarin therapy in the 2-week period, particularly at 7 to 10 days, following initiation of the 3-day regimen of EMEND with each chemotherapy cycle [see Drug Interactions (7.1) ] .
5.3Risk of Reduced Efficacy of Hormonal Contraceptives Upon coadministration with EMEND, the efficacy of hormonal contraceptives may be reduced during administration of and for 28 days following the last dose of EMEND [see Clinical Pharmacology (12.3) ] . Advise patients to use effective alternative or back-up methods of contraception during treatment with EMEND and for 1 month following the last dose of EMEND [see Drug Interactions (7.1) , Use in Specific Populations (8.3) ] .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (≥3%) are ( 6.1 ): Adults: fatigue, diarrhea, asthenia, dyspepsia, abdominal pain, hiccups, white blood cell count decreased, dehydration, and alanine aminotransferase increased. Pediatrics: neutropenia, headache, diarrhea, decreased appetite, cough, fatigue, hemoglobin decreased, dizziness, and hiccups. To report SUSPECTED ADVERSE REACTIONS, contact Merck Sharp & Dohme LLC at 1-877-888-4231 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. The overall safety of EMEND was evaluated in approximately 6800 individuals. Adults In 2 active-controlled, double-blind clinical trials in patients receiving highly emetogenic chemotherapy (HEC) (Studies 1 and 2), EMEND in combination with ondansetron and dexamethasone (EMEND regimen) was compared to ondansetron and dexamethasone alone (standard therapy) [see Clinical Studies (14.1) ] .
In 2 active-controlled clinical trials in patients receiving moderately emetogenic chemotherapy (MEC) (Studies 3 and 4), EMEND in combination with ondansetron and dexamethasone (EMEND regimen) was compared to ondansetron and dexamethasone alone (standard therapy) [see Clinical Studies (14.2) ]. The most common adverse reaction reported in patients who received MEC in pooled Studies 3 and 4 was dyspepsia (6% versus 4%). Across these 4 studies there were 1412 patients treated with the EMEND regimen during Cycle 1 of chemotherapy and 1099 of these patients continued into the Multiple-Cycle extension for up to 6 cycles of chemotherapy.
The most common adverse reactions reported in patients who received HEC and MEC in pooled Studies 1, 2, 3 and 4 are listed in Table 5. Table 5: Most Common Adverse Reactions in Patients Receiving HEC and MEC from a Pooled Analysis of HEC and MEC Studies Reported in ≥ 3% of patients treated with the EMEND regimen and at a greater incidence than standard therapy. EMEND, ondansetron, and dexamethasone EMEND regimen (N=1412) Ondansetron and dexamethasone Standard therapy (N=1396) fatigue 13% 12% diarrhea 9% 8% asthenia 7% 6% dyspepsia 7% 5% abdominal pain 6% 5% hiccups 5% 3% white blood cell count decreased 4% 3% dehydration 3% 2% alanine aminotransferase increased 3% 2% In a pooled analysis of the HEC and MEC studies, less common adverse reactions reported in patients treated with the EMEND regimen are listed in Table 6.
Table 6: Less Common Adverse Reactions in EMEND-Treated Patients from a Pooled Analysis of HEC and MEC Studies Reported in > 0.5% of patients treated with the EMEND regimen, at a greater incidence than standard therapy and not previously described in Table 5. Infection and Infestations oral candidiasis, pharyngitis Blood and the Lymphatic System Disorders anemia, febrile neutropenia, neutropenia, thrombocytopenia Metabolism and Nutrition Disorders decreased appetite, hypokalemia Psychiatric Disorders anxiety Nervous System Disorders dizziness, dysgeusia, peripheral neuropathy Cardiac Disorders palpitations Vascular Disorders flushing, hot flush Respiratory, Thoracic and Mediastinal Disorders cough, dyspnea, oropharyngeal pain Gastrointestinal Disorders dry mouth, eructation, flatulence, gastritis, gastroesophageal reflux disease, nausea, vomiting Skin and Subcutaneous Tissue Disorders alopecia, hyperhidrosis, rash Musculoskeletal and Connective Tissue Disorders musculoskeletal pain General Disorders and Administration Site Condition edema peripheral, malaise Investigations aspartate aminotransferase increased, blood alkaline phosphatase increased, blood sodium decreased, blood urea increased, proteinuria, weight decreased In an additional active-controlled clinical study in 1169 patients receiving EMEND and HEC, the a…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS See Full Prescribing Information for a list of clinically significant drug interactions. ( 4 , 5.1 , 5.2 , 5.3 , 7.1 , 7.2 )
7.1Effect of Aprepitant on the Pharmacokinetics of Other Drugs Aprepitant is a substrate, a weak-to-moderate (dose-dependent) inhibitor, and an inducer of CYP3A4. Aprepitant is also an inducer of CYP2C9 [see Clinical Pharmacology (12.3) ] . Aprepitant acts as a moderate inhibitor of CYP3A4 when administered as a 3-day regimen (125-mg/80-mg/80-mg) and can increase plasma concentrations of concomitant drugs that are substrates for CYP3A4.
Some substrates of CYP3A4 are contraindicated with EMEND [see Contraindications (4) ] . Dosage adjustment of some CYP3A4 and CYP2C9 substrates may be warranted, as shown in Table 8. Table 8: Effects of Aprepitant on the Pharmacokinetics of Other Drugs CYP3A4 Substrates Pimozide Clinical Impact Increased pimozide exposure.
Intervention EMEND is contraindicated [see Contraindications (4) ] . Benzodiazepines Clinical Impact Increased exposure to midazolam or other benzodiazepines metabolized via CYP3A4 (alprazolam, triazolam) may increase the risk of adverse reactions [see Clinical Pharmacology (12.3) ]. Intervention Monitor for benzodiazepine-related adverse reactions.
Depending on the clinical situation (e.g., elderly patients) and degree of monitoring available, reduce the dose of intravenous midazolam Dexamethasone Clinical Impact Increased dexamethasone exposure [see Clinical Pharmacology (12.3) ]. Intervention Reduce the dose of oral dexamethasone by approximately 50% [see Dosage and Administration (2.1) ]. Methylprednisolone Clinical Impact Increased methylprednisolone exposure [see Clinical Pharmacology (12.3) ].
Intervention Reduce the dose of intravenous methylprednisolone by approximately 25% Reduce the dose of oral methylprednisolone by approximately 50% Chemotherapeutic agents that are metabolized by CYP3A4 Clinical Impact Increased exposure of the chemotherapeutic agent may increase the risk of adverse reactions [see Clinical Pharmacology (12.3) ] . Intervention Vinblastine, vincristine, or ifosfamide or other chemotherapeutic agents Monitor for chemotherapeutic-related adverse reactions. Etoposide, vinorelbine, paclitaxel, and docetaxel No dosage adjustment needed.
Hormonal Contraceptives Clinical Impact Decreased hormonal exposure during administration of and for 28 days after administration of the last dose of EMEND [see Warnings and Precautions (5.3) , Use in Specific Populations (8.3) , Clinical Pharmacology (12.3) ] . Intervention Effective alternative or back-up methods of contraception (such as condoms and spermicides) should be used during treatment with EMEND and for 1 month following the last dose of EMEND. Examples birth control pills, skin patches, implants, and certain IUDs CYP2C9 Substrates Warfarin Clinical Impact Decreased warfarin exposure and decreased prothrombin time (INR) [see Warnings and Precautions (5.2) , Clinical Pharmacology (12.3) ] .
Intervention In patients on chronic warfarin therapy, monitor the prothrombin time (INR) in the 2-week period, particularly at 7 to 10 days, following initiation of the 3-day EMEND regimen with each chemotherapy cycle. Other 5-HT 3 Antagonists Clinical Impact No change in the exposure of the 5-HT 3 antagonist [see Clinical Pharmacology (12.3) ] . Intervention No dosage adjustment needed Examples ondansetron, granisetron, dolasetron
7.2Effect of Other Drugs on the Pharmacokinetics of Aprepitant Aprepitant is a CYP3A4 substrate [see Clinical Pharmacology (12.3) ] . Co-administration of EMEND with drugs that are inhibitors or inducers of CYP3A4 may result in increased or decreased plasma concentrations of aprepitant, respectively, as shown in Table 9. Table 9: Effects of Other Drugs on Pharmacokinetics of Aprepitant Moderate to Strong CYP3A4 Inhibitors Clinical Impact Significantly increased exposure of aprepitant may increase the risk of adverse reactions associated with EMEND [see…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are insufficient data on use of EMEND in pregnant women to inform a drug associated risk. In animal reproduction studies, no adverse developmental effects were observed in rats or rabbits exposed during the period of organogenesis to systemic drug levels (AUC) approximately 1.5 times the adult human exposure at the 125-mg/80-mg/80-mg EMEND regimen [see Data ] . The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data In embryofetal development studies in rats and rabbits, aprepitant was administered during the period of organogenesis at oral doses up to 1000 mg/kg twice daily in rats and up to the maximum tolerated dose of 25 mg/kg/day in rabbits. No embryofetal lethality or malformations were observed at any dose level in either species.
The exposures (AUC) in pregnant rats at 1000 mg/kg twice daily and in pregnant rabbits at 125 mg/kg/day were approximately 1.5 times the adult exposure at the 125-mg/80-mg/80-mg EMEND regimen. Aprepitant crosses the placenta in rats and rabbits.
8.2Lactation Risk Summary Lactation studies have not been conducted to assess the presence of aprepitant in human milk, the effects on the breastfed infant, or the effects on milk production. Aprepitant is present in rat milk. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for EMEND and any potential adverse effects on the breastfed infant from EMEND or from the underlying maternal condition.
8.3Females and Males of Reproductive Potential Contraception Upon administration of EMEND, the efficacy of hormonal contraceptives may be reduced. Advise females of reproductive potential using hormonal contraceptives to use an effective alternative or back-up non-hormonal contraceptive (such as condoms and spermicides) during treatment with EMEND and for 1 month following the last dose [see Drug Interactions (7.1) , Clinical Pharmacology (12.3) ] .
8.4Pediatric Use The safety and effectiveness of EMEND for oral suspension have been established in pediatric patients 6 months of age and older and EMEND capsules in pediatric patients 12 years of age and older for the prevention of acute and delayed nausea and vomiting associated with initial and repeat courses of HEC, including high-dose cisplatin, and MEC. Use of EMEND in these age groups is supported by evidence from 302 pediatric patients in a randomized, double-blind, active comparator controlled clinical study (n = 207 patients aged 6 months to less than 12 years, n = 95 patients aged 12 through 17 years).
EMEND was studied in combination with ondansetron with or without dexamethasone (at the discretion of the physician) [see Clinical Studies (14.3) ] . Adverse reactions were similar to those reported in adult patients [see Adverse Reactions (6.1) ] . The safety and effectiveness of EMEND for the prevention of nausea and vomiting associated with HEC or MEC have not been established in patients less than 6 months.
Juvenile Animal Study A study was conducted in young rats to evaluate the effects of aprepitant on growth and on neurobehavioral and sexual development. Rats were treated at oral doses up to the maximum feasible dose of 1000 mg/kg twice daily (providing exposure in male rats lower than the exposure at the recommended pediatric human dose and exposure in female rats equivalent to the pediatric human exposure) from the early postnatal period (Postnatal Day 10) through Postnatal Day 58. Slight changes in the onset of sexual maturation were observed in female and male rats; however, there were no effects on mating, fertility, embryonic-fetal survival, or histomorphology of the reproductive organs.
There were no effects in neurobeh…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are insufficient data on use of EMEND in pregnant women to inform a drug associated risk. In animal reproduction studies, no adverse developmental effects were observed in rats or rabbits exposed during the period of organogenesis to systemic drug levels (AUC) approximately 1.5 times the adult human exposure at the 125-mg/80-mg/80-mg EMEND regimen [see Data ] . The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data In embryofetal development studies in rats and rabbits, aprepitant was administered during the period of organogenesis at oral doses up to 1000 mg/kg twice daily in rats and up to the maximum tolerated dose of 25 mg/kg/day in rabbits. No embryofetal lethality or malformations were observed at any dose level in either species.
The exposures (AUC) in pregnant rats at 1000 mg/kg twice daily and in pregnant rabbits at 125 mg/kg/day were approximately 1.5 times the adult exposure at the 125-mg/80-mg/80-mg EMEND regimen. Aprepitant crosses the placenta in rats and rabbits.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of EMEND for oral suspension have been established in pediatric patients 6 months of age and older and EMEND capsules in pediatric patients 12 years of age and older for the prevention of acute and delayed nausea and vomiting associated with initial and repeat courses of HEC, including high-dose cisplatin, and MEC. Use of EMEND in these age groups is supported by evidence from 302 pediatric patients in a randomized, double-blind, active comparator controlled clinical study (n = 207 patients aged 6 months to less than 12 years, n = 95 patients aged 12 through 17 years).
EMEND was studied in combination with ondansetron with or without dexamethasone (at the discretion of the physician) [see Clinical Studies (14.3) ] . Adverse reactions were similar to those reported in adult patients [see Adverse Reactions (6.1) ] . The safety and effectiveness of EMEND for the prevention of nausea and vomiting associated with HEC or MEC have not been established in patients less than 6 months.
Juvenile Animal Study A study was conducted in young rats to evaluate the effects of aprepitant on growth and on neurobehavioral and sexual development. Rats were treated at oral doses up to the maximum feasible dose of 1000 mg/kg twice daily (providing exposure in male rats lower than the exposure at the recommended pediatric human dose and exposure in female rats equivalent to the pediatric human exposure) from the early postnatal period (Postnatal Day 10) through Postnatal Day 58. Slight changes in the onset of sexual maturation were observed in female and male rats; however, there were no effects on mating, fertility, embryonic-fetal survival, or histomorphology of the reproductive organs.
There were no effects in neurobehavioral tests of sensory function, motor function, and learning and memory.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 544 adult cancer patients treated with EMEND in CINV clinical studies, 31% were aged 65 and over, while 5% were aged 75 and over. Other reported clinical experience with EMEND has not identified differences in responses between elderly and younger patients. In general, use caution when dosing elderly patients as they have a greater frequency of decreased hepatic, renal or cardiac function and concomitant disease or other drug therapy [see Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE No specific information is available on the treatment of overdosage. Drowsiness and headache were reported in one patient who ingested 1440 mg of EMEND (approximately 11 times the maximum recommended single dose). In the event of overdose, EMEND should be discontinued and general supportive treatment and monitoring should be provided.
Because of the antiemetic activity of EMEND, drug-induced emesis may not be effective in cases of EMEND overdosage. Aprepitant is not removed by hemodialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Aprepitant is a selective high-affinity antagonist of human substance P/neurokinin 1 (NK 1 ) receptors. Aprepitant has little or no affinity for serotonin (5-HT 3 ), dopamine, and corticosteroid receptors, the targets of existing therapies for chemotherapy-induced nausea and vomiting (CINV). Aprepitant has been shown in animal models to inhibit emesis induced by cytotoxic chemotherapeutic agents, such as cisplatin, via central actions.
Animal and human Positron Emission Tomography (PET) studies with aprepitant have shown that it crosses the blood brain barrier and occupies brain NK 1 receptors. Animal and human studies show that aprepitant augments the antiemetic activity of the 5-HT 3 -receptor antagonist ondansetron and the corticosteroid dexamethasone and inhibits both the acute and delayed phases of cisplatin-induced emesis.
12.2Pharmacodynamics NK 1 Receptor Occupancy In two single-blind, multiple-dose, randomized, and placebo-controlled studies, healthy young men received oral EMEND doses of 10 mg (N=2), 30 mg (N=3), 100 mg (N=3) or 300 mg (N=5) once daily (0.08, 0.24, 0.8, and 2.4 times the maximum recommended single dose, respectively) for 14 days with 2 or 3 subjects on placebo. Both plasma aprepitant concentration and NK 1 receptor occupancy in the corpus striatum by positron emission tomography were evaluated, at predose and 24 hours after the last dose.
At aprepitant plasma concentrations of approximately 10 ng/mL and 100 ng/mL, the NK 1 receptor occupancies were approximately 50% and 90%, respectively. The oral EMEND regimen produced mean trough plasma aprepitant concentrations greater than 500 ng/mL in adults, which would be expected to, based on the fitted curve with the Hill equation, result in greater than 95% brain NK 1 receptor occupancy. However, the receptor occupancy has not been determined.
In addition, the relationship between NK 1 receptor occupancy and the clinical efficacy of EMEND has not been established. Cardiac Electrophysiology In a randomized, double-blind, positive-controlled, thorough QTc study, a single 200-mg dose of fosaprepitant had no effect on the QTc interval. Maximum aprepitant concentrations after a single 200-mg dose of fosaprepitant were 4-fold higher than that achieved with oral EMEND 125 mg.
QT prolongation with the recommended oral EMEND dosing regimens is not expected.
12.3Pharmacokinetics Absorption Following oral administration of a single 125-mg dose of EMEND on Day 1 and 80 mg once daily on Days 2 and 3, the AUC 0-24hr was approximately 19.6 mcg∙hr/mL and 21.2 mcg∙hr/mL on Day 1 and Day 3, respectively. The C max of 1.6 mcg/mL and 1.4 mcg/mL were reached in approximately 4 hours (T max ) on Day 1 and Day 3, respectively. At the dose range of 80 to 125 mg, the mean absolute oral bioavailability of EMEND is approximately 60 to 65%.
Oral administration of the capsule with a standard high-fat breakfast had no clinically meaningful effect on the bioavailability of aprepitant. The pharmacokinetics of aprepitant were non-linear across the clinical dose range. In healthy young adults, the increase in AUC 0-∞ was 26% greater than dose proportional between 80-mg and 125-mg single doses administered in the fed state.
Distribution Aprepitant is greater than 95% bound to plasma proteins. The mean apparent volume of distribution at steady state (Vd ss ) was approximately 70 L in humans. Aprepitant crosses the blood brain barrier in humans [see Clinical Pharmacology (12.1) ] .
Elimination Metabolism Aprepitant undergoes extensive metabolism. In vitro studies using human liver microsomes indicate that aprepitant is metabolized primarily by CYP3A4 with minor metabolism by CYP1A2 and CYP2C19. Metabolism is largely via oxidation at the morpholine ring and its side chains.
No metabolism by CYP2D6, CYP2C9, or CYP2E1 was detected. In healthy young adults, aprepitant accounts for approximately 24% of the radioactivity in plasma over 72 hours fol…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Aprepitant is a selective high-affinity antagonist of human substance P/neurokinin 1 (NK 1 ) receptors. Aprepitant has little or no affinity for serotonin (5-HT 3 ), dopamine, and corticosteroid receptors, the targets of existing therapies for chemotherapy-induced nausea and vomiting (CINV). Aprepitant has been shown in animal models to inhibit emesis induced by cytotoxic chemotherapeutic agents, such as cisplatin, via central actions.
Animal and human Positron Emission Tomography (PET) studies with aprepitant have shown that it crosses the blood brain barrier and occupies brain NK 1 receptors. Animal and human studies show that aprepitant augments the antiemetic activity of the 5-HT 3 -receptor antagonist ondansetron and the corticosteroid dexamethasone and inhibits both the acute and delayed phases of cisplatin-induced emesis.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING 80-mg capsules: White, opaque, hard gelatin capsule with "461" and "80 mg" printed radially in black ink on the body. They are supplied as follows: NDC 0006-0461-02 unit-of-use BiPack of 2 Unit-of-use TriPack containing one 125-mg capsule and two 80-mg capsules. 125 mg-capsules: Opaque, hard gelatin capsule with white body and pink cap with “462” and “125 mg” printed radially in black ink on the body.
80-mg capsules: White, opaque, hard gelatin capsule with “461” and “80 mg” printed radially in black ink on the body. NDC 0006-3862-03. 125 mg for oral suspension: Pink to light pink powder, in a single-use pouch, packaged as a kit with one 1 mL oral dosing dispenser, one 5 mL oral dosing dispenser, one cap and one mixing cup.
It is supplied as follows: NDC 0006-3066-03 – unit of use carton. Storage and Handling Capsules Store at 20-25°C (68-77°F) [see USP Controlled Room Temperature]. For Oral Suspension Store unopened pouch at 20-25°C (68-77°F); excursions permitted between 15-30°C (between 59-86°F).
Store in the original container. Do not open pouch until ready for use. Once prepared, if suspension is not used immediately, store refrigerated [between 36°F-46°F (2°C-8°C)] for up to 72 hours prior to use.
When ready to use, the mixture can be kept at room temperature [between 68°F-77°F (20°C-25°C)] for up to 3 hours.
📦 Storage and Handling ▾
Storage and Handling Capsules Store at 20-25°C (68-77°F) [see USP Controlled Room Temperature]. For Oral Suspension Store unopened pouch at 20-25°C (68-77°F); excursions permitted between 15-30°C (between 59-86°F). Store in the original container.
Do not open pouch until ready for use. Once prepared, if suspension is not used immediately, store refrigerated [between 36°F-46°F (2°C-8°C)] for up to 72 hours prior to use. When ready to use, the mixture can be kept at room temperature [between 68°F-77°F (20°C-25°C)] for up to 3 hours.
📋 Description ▾
11 DESCRIPTION EMEND capsules contain the active ingredient, aprepitant. Aprepitant is a substance P/neurokinin 1 (NK 1 ) receptor antagonist, an antiemetic agent, chemically described as 5-[[(2 R ,3 S )-2-[(1 R )-1-[3,5-bis(trifluoromethyl)phenyl]ethoxy]-3-(4-fluorophenyl)-4-morpholinyl]methyl]-1,2-dihydro-3 H -1,2,4-triazol-3-one. Its empirical formula is C 23 H 21 F 7 N 4 O 3 , and its structural formula is: Aprepitant is a white to off-white crystalline solid, with a molecular weight of 534.43.
It is practically insoluble in water. Aprepitant is sparingly soluble in ethanol and isopropyl acetate and slightly soluble in acetonitrile. Each capsule of EMEND for oral administration contains either 80 mg or 125 mg of aprepitant and the following inactive ingredients: sucrose, microcrystalline cellulose, hydroxypropyl cellulose and sodium lauryl sulfate.
The capsule shell excipients are gelatin, titanium dioxide, and may contain sodium lauryl sulfate and silicon dioxide. The 125-mg capsule also contains red ferric oxide and yellow ferric oxide. Each pouch of EMEND for oral suspension 125 mg contains 125 mg of aprepitant and the following inactive ingredients: sucrose, lactose, hydroxypropyl cellulose, sodium lauryl sulfate, red iron oxide, and sodium stearyl fumarate.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Hypersensitivity Reactions Advise patients that hypersensitivity reactions, including anaphylaxis, have been reported in patients taking EMEND. Advise patients to stop taking EMEND and seek immediate medical attention if they experience signs or symptoms of a hypersensitivity reaction, such as hives, rash and itching, skin peeling or sores, or difficulty in breathing or swallowing.
Drug Interactions Advise patients to discuss all medications they are taking, including other prescription, non-prescription medication or herbal products [see Contraindications (4) , Warnings and Precautions (5.1) ]. Warfarin: Instruct patients on chronic warfarin therapy to follow instructions from their healthcare provider regarding blood draws to monitor their INR during the 2-week period, particularly at 7 to 10 days, following initiation of the 3-day regimen of EMEND with each chemotherapy cycle [see Warnings and Precautions (5.2) ] .
Hormonal Contraceptives: Advise patients that administration of EMEND may reduce the efficacy of hormonal contraceptives. Instruct patients to use effective alternative or back-up methods of contraception (such as condoms and spermicides) during treatment with EMEND and for 1 month following the last dose of EMEND [see Warnings and Precautions (5.3) , Use in Specific Populations (8.3) ] .