
10 Billion Probiotic with Prebiotic Fiber Blend Ingredients & Drug Interactions
by Safrel
What is this page for?
First and foremost: checking 10 Billion Probiotic with Prebiotic Fiber Blend against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
10 Billion Probiotic with Prebiotic Fiber Blend is a dietary supplement by Safrel with 25 active ingredients. Its ingredients are commonly taken for replacing fluids and electrolytes, preventing dehydration during exercise or illness, treating low blood sodium (under medical care).Based on those ingredients, 1,637 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Turmeric, fresh Ginger, Alfalfa Grass. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against 10 Billion Probiotic with Prebiotic Fiber Blend by Safrel
Ask about any prescription or over-the-counter medication and we check it for interactions with 10 Billion Probiotic with Prebiotic Fiber Blend by Safrel — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of 10 Billion Probiotic with Prebiotic Fiber Blend by Safrel
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Low disclosure
This 36-ingredient blend combines probiotics, prebiotics, and whole-food extracts. The probiotic strains include Lactobacillus acidophilus, Lactobacillus plantarum, Bifidobacterium bifidum, Lactobacillus bulgaricus, Lactobacillus casei, Saccharomyces boulardii, Lactobacillus helveticus, Lactobacillus lactis, Lactobacillus brevis, and Saccharomyces cerevisiae—live microorganisms designed to support gut health.
Prebiotic fiber comes from sources like rice bran, inulin (from alfalfa and chicory), and barley, which feed beneficial bacteria. The formula also includes minerals (sodium, potassium, calcium), plant extracts (turmeric, ginger, spirulina, chlorella, almond, barley grass), and other whole foods (molasses, adzuki bean).
The inactive ingredients are microcrystalline cellulose (a filler) and magnesium stearate (a binder).
Does it work?
Moderate evidence
Evidence for the probiotics themselves is mixed. Lactobacillus acidophilus is possibly effective for irritable bowel syndrome, Helicobacter pylori infection, antibiotic-related diarrhea, and bacterial vaginosis.
Bifidobacterium bifidum is possibly effective for irritable bowel syndrome and respiratory infections. Saccharomyces boulardii is possibly effective for rotaviral diarrhea, traveler's diarrhea, antibiotic-associated diarrhea, and Clostridioides difficile infection.
For the plant ingredients, barley and barley grass are likely effective for high cholesterol and heart disease. Turmeric is possibly effective for depression, high cholesterol, and indigestion.
Ginger is possibly effective for pregnancy-related nausea, menstrual cramps, and osteoarthritis. Spirulina is possibly effective for high blood pressure.
The evidence is insufficient or not established in our data for most other ingredients and many claimed uses.
How safe is it?
Well-documented data
The probiotics are generally well tolerated in healthy people, though mild gastrointestinal side effects like bloating, flatulence, abdominal discomfort, and diarrhea can occur—these are typically uncommon. Calcium is generally safe at recommended amounts, though high doses carry rare risks of kidney stones.
Sodium is essential but excess intake is linked to high blood pressure and kidney strain; normal dietary amounts are fine, but avoid supplementing beyond that. Potassium from food is safe, but supplements can cause dangerously high blood potassium levels, especially in people with kidney disease.
Turmeric can cause indigestion and constipation; rare cases of liver damage have been reported with long-term supplement use. Ginger is generally well tolerated but can cause heartburn and digestive upset at higher doses.
Barley contains gluten. Alfalfa has estrogen-like activity; the safety data advises against it in pregnancy.
Chlorella and spirulina vary widely in purity and may be contaminated with toxins or heavy metals—quality control is inconsistent. Rice bran is likely safe as food, though concentrated supplements are less well studied.
Data on pregnancy and lactation safety are limited or absent for most ingredients; talk with your doctor or pharmacist before use if you are pregnant or breastfeeding.
Meds to double-check
Major interaction found
Double-check this product with your pharmacist if you take blood thinners (warfarin or others), blood pressure medications (especially ACE inhibitors, ARBs, or other antihypertensives), lithium, HIV integrase inhibitors (dolutegravir, elvitegravir), corticosteroids, diabetes medications, immunosuppressants (like tacrolimus), chemotherapy drugs, or antibiotics. The calcium, sodium, potassium, and herbal components can all alter how these drugs work.
The bottom line
Scorecard at a glanceFormula with limited ingredient disclosure with some supporting evidence for its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
This is a multi-ingredient probiotic formula with significant interaction potential, especially if you take blood pressure medications, blood thinners, lithium, or certain HIV drugs—calcium alone requires careful timing. The probiotics themselves may help with specific digestive or infection-related conditions, though evidence is modest.
If you're on any prescription medications, check them against the tool on this page before starting. Otherwise, talk with your pharmacist about whether this product fits your situation and how to take it safely alongside what you're on.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 21 of 36 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Sep 25, 2024.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about 10 Billion Probiotic with Prebiotic Fiber Blend, straight from the product label.
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for 10 Billion Probiotic with Prebiotic Fiber Blend by Safrel, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Sodium | 18.92 mg | 0.88% |
| Potassium | 46.2 mg | 1.32% |
| Calcium | 7.04 mg | 0.86% |
| Carbohydrates | 2.37 Gram(s) | 0.88% |
| Protein | 1.01 Gram(s) | 0.44% |
| Lactobacillus acidophilus | 0 NP | -- |
| Lactobacillus plantarum | 0 NP | -- |
| Bifidobacterium bifidum | 0 NP | -- |
| Lactobacillus bulgaricus | 0 NP | -- |
| Lactobacillus casei | 0 NP | -- |
| Saccharomyces boulardii | 0 NP | -- |
| Spirulina | 0 NP | -- |
| Chlorella | 0 NP | -- |
| Lactobacillus helveticus | 0 NP | -- |
| Rice Bran | 0 NP | -- |
| Lactobacillus lactis | 0 NP | -- |
| Lactobacillus brevis | 0 NP | -- |
| Saccharomyces cerevisiae | 0 NP | -- |
| Turmeric | 0 NP | -- |
| Barley Grass | 0 NP | -- |
| Almond | 0 NP | -- |
| Adzuki Bean | 0 NP | -- |
| Alfalfa Grass | 0 NP | -- |
| Molasses | 0 NP | -- |
| Fat | 0.48 Gram(s) | 0.88% |
| Barley | 0 NP | -- |
| fresh Ginger | 0 NP | -- |
| Oat Grass | 0 NP | -- |
| Probiotic Culture Blend | 0 NP | -- |
| Oat | 0 NP | -- |
| Mung Bean | 0 NP | -- |
| Proprietary Probiotic Herbal Blend | 550 mg | -- |
| Malt | 0 NP | -- |
| Pepitas | 0 NP | -- |
| Sunflower | 0 NP | -- |
| Maize | 0 NP | -- |
| Lactobacillus delbrueckii | 0 NP | -- |
| Lactobacillus caucasicus | 0 NP | -- |
| Lactobacillus fermenti | 0 NP | -- |
| Lactobacillus leichmannii | 0 NP | -- |
Other ingredients: Microcrystalline Cellulose, Magnesium Stearate
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Suggested/Recommended/Usage/Directions
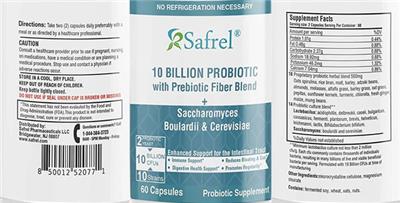
Directions: Take two (2) capsules daily preferably with a meal or as directed by a healthcare professional.
Precautions
Caution Consult a healthcare provider prior to use if pregnant, nursing, on medications, have a medical condition or are planning a medical procedure.
Stop use and contact a physician if adverse reactions occur. Do not use if safety seal is damaged or missing.
Keep out of reach of children.
Contains: fermented soy, wheat, eats, nuts.
Storage
Store in a cool, dry place. Keep bottle tightly closed.
FDA Disclaimer Statement
This statement has not been evaluated by the Food and Drug Administration (FDA). This product is not intended to diagnose, treat, cure or prevent any disease.
General Statements
Questions or comments? Call 1-844-384-3723 9 AM - 5 PM Monday - Friday
Formula
Saccharomyces Boulardii & Cerevisiae 2 probiotic yeast 10 billion CFUs 10 strains
Formulation
Enhanced support the intestinal tract Immune support Digestive health support Reduces bloating & gas Promotes regularity
FDA Statement of Identity
Probiotic Supplement
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
10 Billion Probiotic with Prebiotic Fiber Blend by Safrel label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in 10 Billion Probiotic with Prebiotic Fiber Blend by Safrel
These are the 25 active ingredients this product is made of. Select any to open its full monograph.
Serving size2 Capsule(s) Dosage formCapsule Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Sodium
Interacts with205 drugs
Sodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets g...
Sodium monograph & interactionsPotassium
Interacts with62 drugs
Potassium is an essential mineral your body needs for nerve signals, muscle function, and a steady heartbeat, and most people get enough from a balanc...
Potassium monograph & interactionsCalcium
Interacts with168 drugs
Calcium is an essential mineral your body needs for strong bones, nerve signaling, and muscle function, and supplements can help fill gaps when diet f...
Calcium monograph & interactionsCarbohydrates
Protein
Fat
Probiotic Culture Blend
Interacts with182 drugs
Lactobacillus acidophilus is a 'friendly' bacterium used as a probiotic to support gut and vaginal health. It is generally well tolerated in healthy p...
Probiotic Culture Blend monograph & interactions- › Lactobacillus acidophilus
- › Lactobacillus plantarum
- › Bifidobacterium bifidum
- › Lactobacillus bulgaricus
- › Lactobacillus casei
- › Saccharomyces boulardii
- › Lactobacillus helveticus
- › Lactobacillus lactis
- › Lactobacillus brevis
- › Saccharomyces cerevisiae
- › Lactobacillus delbrueckii
- › Lactobacillus caucasicus
- › Lactobacillus fermenti
- › Lactobacillus leichmannii
Proprietary Probiotic Herbal Blend
- › Spirulina
- › Chlorella
- › Rice Bran
- › Turmeric
- › Barley Grass
- › Almond
- › Adzuki Bean
- › Alfalfa Grass
- › Molasses
- › Barley
- › Fresh Ginger
- › Oat Grass
- › Oat
- › Mung Bean
- › Malt
- › Pepitas
- › Sunflower
- › Maize
Other (inactive) ingredients: Microcrystalline Cellulose, Magnesium Stearate. These complete the product’s ingredient list but are not active constituents.
10 Billion Probiotic with Prebiotic Fiber Blend by Safrel Drug Interactions
HelloPharmacist Interaction Report
Safrel's 10 Billion Probiotic with Prebiotic Fiber Blend contains several ingredients with documented interactions.
The most serious is calcium, which has Major-severity interactions with three HIV integrase inhibitors—dolutegravir, elvitegravir, and the antibiotic ceftriaxone. Calcium can reduce blood levels of these medications by up to 40%, potentially compromising their effectiveness; you'll need to separate dosing by hours to avoid this.
Read the full breakdown — every affected drug type, severity by severity
Moderate-severity interactions span multiple drug classes. Sodium can interfere with blood pressure medications (antihypertensives), lithium (a mood stabilizer), and corticosteroids, among others—high sodium intake may raise blood pressure or cause dangerous electrolyte shifts.
Potassium can increase the risk of dangerously high blood potassium levels when combined with blood pressure drugs like ACE inhibitors or ARBs, particularly at higher supplement doses. Turmeric interacts with chemotherapy drugs, the immunosuppressant tacrolimus, and several others including the breast cancer drug tamoxifen.
Alfalfa grass contains vitamin K and may weaken warfarin (a blood thinner); it also has estrogen-like effects that could interfere with hormonal birth control or hormone therapy. Ginger may increase bleeding risk with blood thinners and blood pressure medications.
Spirulina theoretically interacts with blood thinners, immune-suppressing drugs, and diabetes medications. Chlorella may reduce warfarin's effectiveness due to its vitamin K content, and barley and barley grass have one documented interaction with a parasite drug.
Saccharomyces boulardii (a probiotic yeast) interacts with antifungals at Minor severity. Several probiotic bacteria—Lactobacillus acidophilus, Bifidobacterium bifidum, and Lactobacillus helveticus—may lose effectiveness if taken simultaneously with antibiotics, since the antibiotics can kill the live organisms.
Rice bran has no known interactions documented in our data. We could not check Lactobacillus plantarum, Lactobacillus casei, Lactobacillus bulgaricus, Lactobacillus lactis, Lactobacillus brevis, Saccharomyces cerevisiae, Molasses, Fat, and Adzuki Bean for interactions.
Altogether, these interactions span 1,609 individual medications. Please use the medication checker on this page to verify your exact prescriptions before starting this product.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against 10 Billion Probiotic with Prebiotic Fiber Blend?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in 10 Billion Probiotic with Prebiotic Fiber Blend interact with 1,637 drugs. Click any drug to see the details.
12 of the 25 ingredients in 10 Billion Probiotic with Prebiotic Fiber Blend interact with drugs. Each result below shows which ingredient is responsible. Turmeric fresh Ginger Alfalfa Grass Chlorella Spirulina Sodium Probiotic Culture Blend Calcium Oat Grass Potassium Barley Grass Pepitas
AmphetamineAdensys XR-ODT, Adzenys ER, Dyanavel XR, Mydayis
How Amphetamine interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 1 ingredient. Tap an ingredient for the detail:
Saccharomyces CerevisiaeMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, taking brewer's yeast with MAOIs might increase the risk of hypertension.
Read the full Saccharomyces Cerevisiae + Amphetamine interactionCeftriaxoneRocephin
How Ceftriaxone interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 5 ingredients. Tap an ingredient for the detail:
CalciumCeftriaxone (rocephin) Major
Interaction Summary
Co-administration of intravenous calcium and ceftriaxone can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys.
Read the full Calcium + Ceftriaxone interactionLactobacillus DelbrueckiiAntibiotic Drugs Moderate
Interaction Summary
Theoretically, taking Lactobacillus delbrueckii with antibiotic drugs might decrease the effectiveness of L.
Read the full Lactobacillus Delbrueckii + Ceftriaxone interactionLactobacillus HelveticusAntibiotic Drugs Moderate
Interaction Summary
Theoretically, taking Lactobacillus helveticus with antibiotic drugs might decrease the effectiveness of L.
Read the full Lactobacillus Helveticus + Ceftriaxone interactionBifidobacterium BifidumAntibiotic Drugs Moderate
Interaction Summary
Theoretically, taking Bifidobacterium.
Read the full Bifidobacterium Bifidum + Ceftriaxone interactionProbiotic Culture BlendAntibiotic Drugs Moderate
Interaction Summary
Theoretically, taking Lactobacillus acidophilus with antibiotic drugs might decrease the effectiveness of L.
Read the full Probiotic Culture Blend + Ceftriaxone interactionCobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide FumarateGenvoya
How Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 3 ingredients. Tap an ingredient for the detail:
CalciumElvitegravir (vitekta), Bictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Major
Interaction Summary
Calcium seems to reduce levels of elvitegravir.
Read the full Calcium + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionTurmericHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionFresh GingerP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase the absorption and blood levels of P-glycoprotein (P-gp) substrates.
Read the full Fresh Ginger + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionDolutegravirTivicay
How Dolutegravir interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 3 ingredients. Tap an ingredient for the detail:
CalciumDolutegravir (tivicay) Major
Interaction Summary
Calcium seems to reduce levels of dolutegravir.
Read the full Calcium + Dolutegravir interactionFresh GingerP-glycoprotein Substrates Moderate
Interaction Summary
Ginger might increase the absorption and blood levels of P-glycoprotein (P-gp) substrates.
Read the full Fresh Ginger + Dolutegravir interactionTurmericP-glycoprotein Substrates Minor
Interaction Summary
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
Read the full Turmeric + Dolutegravir interactionDolutegravir, Emtricitabine, Tenofovir AlafenamideDolutegravir, Emtricitabine, Tenofovir Alafenamide
How Dolutegravir, Emtricitabine, Tenofovir Alafenamide interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 3 ingredients. Tap an ingredient for the detail:
CalciumDolutegravir (tivicay), Bictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Major
Interaction Summary
Calcium seems to reduce levels of dolutegravir.
Read the full Calcium + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionTurmericP-glycoprotein Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
Read the full Turmeric + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionFresh GingerP-glycoprotein Substrates Moderate
Interaction Summary
Ginger might increase the absorption and blood levels of P-glycoprotein (P-gp) substrates.
Read the full Fresh Ginger + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionDolutegravir, RilpivirineJuluca
How Dolutegravir, Rilpivirine interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 3 ingredients. Tap an ingredient for the detail:
CalciumDolutegravir (tivicay) Major
Interaction Summary
Calcium seems to reduce levels of dolutegravir.
Read the full Calcium + Dolutegravir, Rilpivirine interactionFresh GingerP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase the absorption and blood levels of P-glycoprotein (P-gp) substrates.
Read the full Fresh Ginger + Dolutegravir, Rilpivirine interactionTurmericP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
Read the full Turmeric + Dolutegravir, Rilpivirine interactionElvitegravirVitekta
How Elvitegravir interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 3 ingredients. Tap an ingredient for the detail:
CalciumElvitegravir (vitekta) Major
Interaction Summary
Calcium seems to reduce levels of elvitegravir.
Read the full Calcium + Elvitegravir interactionFresh GingerCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Fresh Ginger + Elvitegravir interactionTurmericCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric + Elvitegravir interactionElvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil FumarateStribild
How Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 3 ingredients. Tap an ingredient for the detail:
CalciumElvitegravir (vitekta), Bictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Major
Interaction Summary
Calcium seems to reduce levels of elvitegravir.
Read the full Calcium + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionTurmericCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionFresh GingerCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Fresh Ginger + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionIsocarboxazidMarplan
How Isocarboxazid interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 1 ingredient. Tap an ingredient for the detail:
Saccharomyces CerevisiaeMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, taking brewer's yeast with MAOIs might increase the risk of hypertension.
Read the full Saccharomyces Cerevisiae + Isocarboxazid interactionMoclobemideManerix, Moclobemide
How Moclobemide interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 1 ingredient. Tap an ingredient for the detail:
Saccharomyces CerevisiaeMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, taking brewer's yeast with MAOIs might increase the risk of hypertension.
Read the full Saccharomyces Cerevisiae + Moclobemide interactionOzanimod HydrochlorideZeposia
How Ozanimod Hydrochloride interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 4 ingredients. Tap an ingredient for the detail:
Saccharomyces CerevisiaeMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, taking brewer's yeast with MAOIs might increase the risk of hypertension.
Read the full Saccharomyces Cerevisiae + Ozanimod Hydrochloride interactionTurmericHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric + Ozanimod Hydrochloride interactionAlfalfa GrassImmunosuppressants Moderate
Interaction Summary
Theoretically, alfalfa might decrease the efficacy of immunosuppressive therapy.
Read the full Alfalfa Grass + Ozanimod Hydrochloride interactionSpirulinaImmunosuppressants Moderate
Interaction Summary
Theoretically, concurrent use of blue-green algae might interfere with immunosuppressive therapy.
Read the full Spirulina + Ozanimod Hydrochloride interactionPhenelzine SulfateNardil
How Phenelzine Sulfate interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 1 ingredient. Tap an ingredient for the detail:
Saccharomyces CerevisiaeMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, taking brewer's yeast with MAOIs might increase the risk of hypertension.
Read the full Saccharomyces Cerevisiae + Phenelzine Sulfate interactionRasagilineAzilect
How Rasagiline interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 5 ingredients. Tap an ingredient for the detail:
Saccharomyces CerevisiaeMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, taking brewer's yeast with MAOIs might increase the risk of hypertension.
Read the full Saccharomyces Cerevisiae + Rasagiline interactionChlorellaPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, chlorella might have additive effects with photosensitizing drugs.
Read the full Chlorella + Rasagiline interactionAlfalfa GrassPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa Grass + Rasagiline interactionFresh GingerCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Fresh Ginger + Rasagiline interactionTurmericCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric + Rasagiline interactionSafinamide MesylateXadago
How Safinamide Mesylate interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 1 ingredient. Tap an ingredient for the detail:
Saccharomyces CerevisiaeMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, taking brewer's yeast with MAOIs might increase the risk of hypertension.
Read the full Saccharomyces Cerevisiae + Safinamide Mesylate interactionSelegilineCarbex, Eldepryl, Emsam, Zelapar
How Selegiline interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 3 ingredients. Tap an ingredient for the detail:
Saccharomyces CerevisiaeMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, taking brewer's yeast with MAOIs might increase the risk of hypertension.
Read the full Saccharomyces Cerevisiae + Selegiline interactionChlorellaPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, chlorella might have additive effects with photosensitizing drugs.
Read the full Chlorella + Selegiline interactionAlfalfa GrassPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa Grass + Selegiline interactionTranylcypromineParnate
How Tranylcypromine interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 1 ingredient. Tap an ingredient for the detail:
Saccharomyces CerevisiaeMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, taking brewer's yeast with MAOIs might increase the risk of hypertension.
Read the full Saccharomyces Cerevisiae + Tranylcypromine interactionWarfarinWarfarin
How Warfarin interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 5 ingredients. Tap an ingredient for the detail:
Alfalfa GrassWarfarin (coumadin) Major
Interaction Summary
Theoretically, alfalfa might reduce the anticoagulant activity of warfarin.
Read the full Alfalfa Grass + Warfarin interactionTurmericCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +2 Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric + Warfarin interactionFresh GingerCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2c9 (cyp2c9) Substrates +3 Moderate
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Fresh Ginger + Warfarin interactionChlorellaWarfarin (coumadin) Moderate
Interaction Summary
Theoretically, chlorella might reduce the clinical effects of warfarin.
Read the full Chlorella + Warfarin interactionSpirulinaAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, spirulina blue-green algae might increase the risk of bleeding if used with other anticoagulant or antiplatelet drugs.
Read the full Spirulina + Warfarin interactionWarfarin SodiumCoumadin, Panwarfin, Sofarin
How Warfarin Sodium interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 5 ingredients. Tap an ingredient for the detail:
Alfalfa GrassWarfarin (coumadin) Major
Interaction Summary
Theoretically, alfalfa might reduce the anticoagulant activity of warfarin.
Read the full Alfalfa Grass + Warfarin Sodium interactionTurmericAnticoagulant/antiplatelet Drugs, Warfarin (coumadin) +2 Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric + Warfarin Sodium interactionFresh GingerWarfarin (coumadin), Cytochrome P450 1a2 (cyp1a2) Substrates +3 Moderate
Interaction Summary
Ginger might increase the risk of bleeding with warfarin.
Read the full Fresh Ginger + Warfarin Sodium interactionChlorellaWarfarin (coumadin) Moderate
Interaction Summary
Theoretically, chlorella might reduce the clinical effects of warfarin.
Read the full Chlorella + Warfarin Sodium interactionSpirulinaAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, spirulina blue-green algae might increase the risk of bleeding if used with other anticoagulant or antiplatelet drugs.
Read the full Spirulina + Warfarin Sodium interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 3 ingredients. Tap an ingredient for the detail:
SpirulinaImmunosuppressants Moderate
Interaction Summary
Theoretically, concurrent use of blue-green algae might interfere with immunosuppressive therapy.
Read the full Spirulina + 6-mercaptopurine interactionTurmericHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric + 6-mercaptopurine interactionAlfalfa GrassImmunosuppressants Moderate
Interaction Summary
Theoretically, alfalfa might decrease the efficacy of immunosuppressive therapy.
Read the full Alfalfa Grass + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 2 ingredients. Tap an ingredient for the detail:
Fresh GingerCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Fresh Ginger + Ado-trastuzumab Emtansine interactionTurmericCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 1 ingredient. Tap an ingredient for the detail:
TurmericHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 1 ingredient. Tap an ingredient for the detail:
TurmericHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric + Abacavir, Lamivudine interactionAbciximabReoPro
How Abciximab interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 3 ingredients. Tap an ingredient for the detail:
SpirulinaAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, spirulina blue-green algae might increase the risk of bleeding if used with other anticoagulant or antiplatelet drugs.
Read the full Spirulina + Abciximab interactionFresh GingerAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Ginger may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Fresh Ginger + Abciximab interactionTurmericAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 2 ingredients. Tap an ingredient for the detail:
TurmericCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric + Abemaciclib interactionFresh GingerCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Fresh Ginger + Abemaciclib interactionAbiraterone
How Abiraterone interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 2 ingredients. Tap an ingredient for the detail:
Fresh GingerCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Fresh Ginger + Abiraterone interactionTurmericCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 2 ingredients. Tap an ingredient for the detail:
TurmericHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric + Abiraterone Acetate interactionFresh GingerCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Fresh Ginger + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 4 ingredients. Tap an ingredient for the detail:
TurmericAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric + Abrocitinib interactionAlfalfa GrassImmunosuppressants Moderate
Interaction Summary
Theoretically, alfalfa might decrease the efficacy of immunosuppressive therapy.
Read the full Alfalfa Grass + Abrocitinib interactionSpirulinaImmunosuppressants, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, concurrent use of blue-green algae might interfere with immunosuppressive therapy.
Read the full Spirulina + Abrocitinib interactionFresh GingerCytochrome P450 2c9 (cyp2c9) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, ginger might increase the levels of CYP2C9 substrates.
Read the full Fresh Ginger + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 2 ingredients. Tap an ingredient for the detail:
TurmericP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
Read the full Turmeric + Acalabrutinib interactionFresh GingerCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Fresh Ginger + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 6 ingredients. Tap an ingredient for the detail:
SpirulinaAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking blue-green algae with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Spirulina + Acarbose interactionFresh GingerAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking ginger with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Fresh Ginger + Acarbose interactionAlfalfa GrassAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, alfalfa might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Read the full Alfalfa Grass + Acarbose interactionTurmericHepatotoxic Drugs, Antidiabetes Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric + Acarbose interactionSaccharomyces CerevisiaeAntidiabetes Drugs Moderate
Interaction Summary
Taking brewer's yeast with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Saccharomyces Cerevisiae + Acarbose interactionOatAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, oats may have additive effects with antidiabetic agents and might increase the risk of hypoglycemia.
Read the full Oat + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with 10 Billion Probiotic with Prebiotic Fiber Blend — through 2 ingredients. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Acebutolol interactionTurmericHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric + Acebutolol interactionEach ingredient & the kinds of drugs it affects
For each ingredient in 10 Billion Probiotic with Prebiotic Fiber Blend with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Turmeric
Alkylating Agents
Turmeric has antioxidant effects. Theoretically, this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro research suggests that curcumin, a constituent of turmeric, inhibits mechlorethamine-induced apoptosis of breast cancer cells by up to 70%. Also, animal research shows that curcumin inhibits cyclophosphamide-induced tumor regression. However, some in vitro research shows that curcumin does not affect the apoptosis capacity of etoposide. Also, other laboratory research suggests that curcumin might augment the cytotoxic effects of alkylating agents. Reasons for the discrepancies may relate to the dose of curcumin and the specific chemotherapeutic agent. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effect, if any, turmeric might have on alkylating agents.
Amlodipine (Norvasc)
Taking turmeric with amlodipine may increase levels of amlodipine.
Animal research shows that giving amlodipine 1 mg/kg as a single dose following the use of turmeric extract 200 mg/kg daily for 2 weeks increases the maximum concentration and area under the curve by 53% and 56%, respectively, when compared with amlodipine alone. Additional animal research shows that taking amlodipine 1 mg/kg with a curcumin 2 mg/kg pretreatment for 10 days increases the maximum concentration and area under the curve by about 2-fold when compared with amlodipine alone.
Anticoagulant/Antiplatelet Drugs
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs. However, research is conflicting.
Curcumin, a constituent of turmeric, has demonstrated antiplatelet effects in vitro. Furthermore, two case reports have found that taking turmeric along with warfarin or fluindione was associated with an increased international normalized ratio (INR). However, one clinical study in healthy volunteers shows that taking curcumin 500 mg daily for 3 weeks, alone or with aspirin 100 mg, does not increase antiplatelet effects or bleeding risk. It is possible that the dose of turmeric used in this study was too low to produce a notable effect.
Antidiabetes Drugs
Theoretically, taking turmeric with antidiabetes drugs might increase the risk of hypoglycemia.
Animal research and case reports suggest that curcumin, a turmeric constituent, can reduce blood glucose levels in patients with diabetes. Furthermore, clinical research in adults with type 2 diabetes shows that taking curcumin 475 mg daily for 10 days prior to taking glyburide 5 mg decreased postprandial glucose levels for up to 24 hours when compared with glyburide alone, despite the lack of a significant pharmacokinetic interaction. Other clinical studies in patients with diabetes show that taking curcumin daily can reduce blood glucose levels when compared with placebo.
Antitumor Antibiotics
Turmeric has antioxidant effects. Theoretically, this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro and animal research shows that curcumin, a constituent of turmeric, inhibits doxorubicin-induced apoptosis of breast cancer cells by up to 65%. However, curcumin does not seem to affect the apoptosis capacity of daunorubicin. In fact, some research shows that curcumin might augment the cytotoxic effects of antitumor antibiotics, increasing their effectiveness. Reasons for the discrepancies may relate to the dose of curcumin and the chemotherapeutic agent. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effects, if any, antioxidants such as turmeric have on antitumor antibiotics.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
In vitro and animal research show that turmeric and its constituents curcumin and curcuminoids inhibit CYP3A4. Also, 8 case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking turmeric and cancer medications that are CYP3A4 substrates, including everolimus, ruxolitinib, ibrutinib, and palbociclib, and bortezomib. In another case report, a transplant patient presented with acute nephrotoxicity and elevated tacrolimus levels after consuming turmeric powder at a dose of 15 or more spoonfuls daily for ten days prior. It was thought that turmeric increased levels of tacrolimus due to CYP3A4 inhibition.
Conversely, other in vitro research suggests that turmeric induces CYP3A4 activity, leading to reduced levels of CYP3A4 substrates. An animal model suggests that induction of CYP3A4 occurs after daily curcumin use for 1 week. However, the induction of CYP3A4 by turmeric has not been reported in humans.
Hepatotoxic Drugs
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
There is concern that turmeric might cause hepatotoxicity, especially when highly bioavailable formulations are used in high doses.
Methotrexate (Trexall, Others)
Theoretically, turmeric might have additive effects when used with hepatotoxic drugs such as methotrexate.
In one case report, a 39-year-old female taking methotrexate, turmeric, and linseed oil developed hepatotoxicity.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Theoretically, turmeric might increase blood levels of OATP4C1 substrates.
In vitro research shows that the turmeric constituent curcumin competitively inhibits OATP4C1 transport. This transporter is expressed in the kidney and facilitates the renal excretion of certain drugs. Theoretically, taking turmeric might decrease renal excretion of OATP substrates.
Sulfasalazine (Azulfidine)
Turmeric might increase the effects and adverse effects of sulfasalazine.
Clinical research shows that taking the turmeric constituent, curcumin, can increase blood levels of sulfasalazine by 3.2-fold.
Tacrolimus (Prograf)
Turmeric might increase the effects and adverse effects of tacrolimus.
In one case report, a transplant patient presented with acute nephrotoxicity and elevated tacrolimus levels of 29 ng/mL. The patient previously had tacrolimus levels within the therapeutic range at 9.7 ng/mL. Ten days prior to presenting at the emergency room the patient started consumption of turmeric powder at a dose of 15 or more spoonfuls daily. It was thought that turmeric increased levels of tacrolimus due to cytochrome P450 3A4 (CYP3A4) inhibition. In vitro and animal research show that turmeric and its constituent curcumin inhibit CYP3A4.
Talinolol
Turmeric may reduce the absorption of talinolol in some situations.
Clinical research shows that taking curcumin for 6 days decreases the bioavailability of talinolol when taken together on the seventh day. The clinical significance of this effect is unclear.
Tamoxifen (Nolvadex)
Theoretically, turmeric might reduce the levels and clinical effects of tamoxifen.
In a small clinical trial in patients with breast cancer taking tamoxifen 20-30 mg daily, adding curcumin 1200 mg plus piperine 10 mg three times daily reduces the 24-hour area under the curve of tamoxifen and the active metabolite endoxifen by 12.8% and 12.4%, respectively, as well as the maximum concentrations of tamoxifen, when compared with tamoxifen alone. However, in the absence of piperine, the area under the curve for endoxifen and the maximum concentration of tamoxifen were not significantly reduced. Effects were most pronounced in patients who were extensive cytochrome P450 (CYP) 2D6 metabolizers.
Topoisomerase I Inhibitors
Turmeric has antioxidant effects. There is some concern that this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro research shows that curcumin, a constituent of turmeric, inhibits camptothecin-induced apoptosis of breast cancer cells by up to 71%. However, other in vitro research shows that curcumin augments the cytotoxic effects of camptothecin. Reasons for the discrepancies may relate to the dose of curcumin and the chemotherapeutic agents. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effect, if any, turmeric might have.
Tramadol (Ultram)
Theoretically, turmeric might increase or decrease levels of tramadol.
Animal research suggests that a single dose of curcumin, a constituent of turmeric, may increase tramadol's maximum concentration (Cmax) by inhibiting metabolism, while continued daily use for 7 days may reduce the area under the curve (AUC) due to the induction of drug-metabolizing enzymes such as cytochrome P450 3A4 (CYP3A4). However, this interaction has not been reported in humans.
Warfarin (Coumadin)
Turmeric might increase the risk of bleeding with warfarin.
One case of increased international normalized ratio (INR) has been reported for a patient taking warfarin who began taking turmeric. Prior to taking turmeric, the patient had stable INR measurements. Within a few weeks of starting turmeric supplementation, the patient's INR increased to 10. Additionally, curcumin, the active constituent in turmeric, has demonstrated antiplatelet effects in vitro, which may produce additive effects when taken with warfarin.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2. However, research is conflicting.
In vitro and animal research show that the turmeric constituent, curcumin, inhibits CYP1A2. However, other in vitro research suggests that curcumin does not significantly affect CYP1A2.
Docetaxel (Taxotere)
Theoretically, turmeric might increase blood levels of oral docetaxel.
Animal research suggests that the turmeric constituent, curcumin, enhances the oral bioavailability of docetaxel. However, the significance of this interaction is unclear, as this drug is typically administered intravenously in clinical settings.
Estrogens
Theoretically, large amounts of turmeric might interfere with hormone replacement therapy through competition for estrogen receptors.
In vitro research shows that curcumin, a constituent of turmeric, displaces the binding of estrogen to its receptors.
Glyburide (Diabeta, Others)
Theoretically, taking turmeric and glyburide in combination might increase the risk of hypoglycemia.
Clinical research shows that taking curcumin 475 mg daily for 10 days prior to taking glyburide 5 mg increases blood levels of glyburide by 12% at 2 hours after the dose in patients with type 2 diabetes. While maximal blood concentrations of glyburide were not affected, turmeric modestly decreased postprandial glucose levels for up to 24 hours when compared to glyburide alone, possibly due to the hypoglycemic effect of turmeric demonstrated in animal research.
Losartan (Cozaar)
Theoretically, turmeric might increase the effects of losartan.
Research in hypertensive rats shows that taking turmeric can increase the hypotensive effects of losartan.
Norfloxacin (Noroxin)
Theoretically, turmeric might increase the effects and adverse effects of norfloxacin.
Animal research shows that taking curcumin, a turmeric constituent, can increase blood levels of orally administered norfloxacin.
P-Glycoprotein Substrates
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
In vitro and animal research shows that curcuminoids and other constituents found in turmeric can inhibit P-glycoprotein expression and activity.
Paclitaxel (Abraxane, Onxol)
Theoretically, turmeric might alter blood levels of paclitaxel, although any effect may not be clinically relevant.
Clinical research in adults with breast cancer receiving intravenous paclitaxel suggests that taking turmeric may modestly alter paclitaxel pharmacokinetics. Patients received paclitaxel on day 1, followed by either no treatment or turmeric 2 grams daily from days 2-22. Pharmacokinetic modeling suggests that turmeric reduces the maximum concentration and area under the curve of paclitaxel by 12.1% and 7.7%, respectively. However, these changes are not likely to be considered clinically relevant. Conversely, animal research suggests that curcumin, a constituent of turmeric, enhances the oral bioavailability of paclitaxel. However, the significance of this interaction is unclear, as this drug is typically administered intravenously in clinical settings.
fresh Ginger
Anticoagulant/Antiplatelet Drugs
Ginger may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs. However, research is conflicting.
Laboratory research suggests that ginger inhibits thromboxane synthetase and decreases platelet aggregation. However, this has not been demonstrated unequivocally in humans, with mixed results from clinical trials. Theoretically, excessive amounts of ginger might increase the risk of bleeding when used with anticoagulant/antiplatelet drugs.
Antidiabetes Drugs
Theoretically, taking ginger with antidiabetes drugs might increase the risk of hypoglycemia.
Animal and human research suggests that ginger might increase insulin levels and/or decrease blood glucose levels.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Ginger might increase or decrease the levels of CYP3A4 substrates.
In vitro research and some case reports suggest that ginger inhibits CYP3A4 activity. Three case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking ginger and cancer medications that are CYP3A4 substrates (imatinib, dabrafenib, and crizotinib). However, the causality of this interaction is unclear due to the presence of multiple interacting drugs and routes of administration.
Conversely, other in vitro research suggests that ginger induces CYP3A4 activity, leading to reduced levels of CYP3A4 substrates. However, this interaction has not been reported in humans.
Losartan (Cozaar)
Theoretically, ginger might increase levels of losartan and the risk of hypotension.
In animal research, ginger increased the levels and hypotensive effects of a single dose of losartan. It is not clear if ginger alters the concentration or effects of losartan when taken continuously. Additionally, this interaction has not been shown in humans.
Nifedipine (Procardia)
Ginger may have antiplatelet effects and increase the risk of bleeding if used with nifedipine.
Clinical research shows that combined treatment with ginger 1 gram plus nifedipine 10 mg significantly inhibits platelet aggregation when compared to nifedipine or ginger alone.
P-Glycoprotein Substrates
Ginger might increase the absorption and blood levels of P-glycoprotein (P-gp) substrates.
In vitro research and case reports suggest that ginger inhibits drug efflux by P-gp, potentially increasing absorption and serum levels of P-gp substrates. Two case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking ginger and cancer medications that are P-gp substrates (trametinib, crizotinib). However, the causality of this interaction is unclear due to the presence of multiple interacting drugs and routes of administration.
Phenprocoumon (Marcoumar, Others)
Ginger might increase the risk of bleeding with phenprocoumon.
Phenprocoumon, a warfarin-related anticoagulant, might increase the international normalized ratio (INR) when taken with ginger. There is one case report of a 76-year-old woman with a stable INR on phenprocoumon that increased to greater than 10 when she began consuming dried ginger and ginger tea.
Warfarin (Coumadin)
Ginger might increase the risk of bleeding with warfarin.
Laboratory research suggests that ginger might inhibit thromboxane synthetase and decrease platelet aggregation. In one case report, ginger increased the INR when taken with phenprocoumon, which has similar pharmacological effects as warfarin. In another case report, ginger increased the INR when taken with a combination of warfarin, hydrochlorothiazide, and acetaminophen. A longitudinal analysis suggests that taking ginger increases the risk of bleeding in patients taking warfarin for at least 4 months. However, research in healthy people suggests that ginger has no effect on INR, or the pharmacokinetics or pharmacodynamics of warfarin. Until more is known, monitor INRs closely in patients taking large amounts of ginger.
Calcium Channel Blockers
Theoretically, taking ginger with calcium channel blockers might increase the risk of hypotension.
Some animal and in vitro research suggests that ginger has hypotensive and calcium channel-blocking effects. Another animal study shows that concomitant administration of ginger and the calcium channel blocker amlodipine leads to greater reductions in blood pressure when compared with amlodipine alone.
Cyclosporine (Neoral, Sandimmune)
Theoretically, when taken prior to cyclosporine, ginger might decrease cyclosporine levels.
In an animal model, ginger juice taken 2 hours prior to cyclosporine administration reduced the maximum concentration and area under the curve of cyclosporine by 51% and 40%, respectively. This effect was not observed when ginger juice and cyclosporine were administered at the same time.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, ginger might increase the levels of CYP1A2 substrates.
In vitro research shows that ginger inhibits CYP1A2 activity. However, this interaction has not been reported in humans.
Cytochrome P450 2B6 (Cyp2B6) Substrates
Theoretically, ginger might increase the levels of CYP2B6 substrates.
In vitro research shows that ginger inhibits CYP2B6 activity. However, this interaction has not been reported in humans.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, ginger might increase the levels of CYP2C9 substrates.
In vitro research shows that ginger inhibits CYP2C9 activity. However, this interaction has not been reported in humans.
Metronidazole (Flagyl)
Theoretically, ginger might increase levels of metronidazole.
In an animal model, ginger increased the absorption and plasma half-life of metronidazole. In addition, the elimination rate and clearance of metronidazole was significantly reduced.
Alfalfa Grass
Warfarin (Coumadin)
Theoretically, alfalfa might reduce the anticoagulant activity of warfarin.
Alfalfa contains a large amount of vitamin K. This could theoretically interfere with the activity of warfarin.
Antidiabetes Drugs
Theoretically, alfalfa might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Animal research suggests that alfalfa decreases blood sugar in diabetic mice. Also, in one case report, a diabetic patient experienced hypoglycemia after consuming alfalfa extract. Monitor blood glucose levels closely. Dose adjustments might be necessary.
Contraceptive Drugs
Theoretically, alfalfa might interfere with the activity of contraceptive drugs.
Alfalfa contains coumestrol, a phytoestrogen, and isoflavonoids, which have estrogenic effects.
Estrogens
Theoretically, alfalfa might interfere with hormone therapy.
Alfalfa contains coumestrol, a phytoestrogen, and isoflavonoids, which have estrogenic effects.
Immunosuppressants
Theoretically, alfalfa might decrease the efficacy of immunosuppressive therapy.
In vitro research and human case reports suggest that alfalfa may have immunostimulant effects.
Photosensitizing Drugs
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Animal research suggests that excessive doses of alfalfa may increase photosensitivity, possibly due to its chlorophyll content. It is unclear if this effect would be clinically relevant in humans.
Chlorella
Photosensitizing Drugs
Theoretically, chlorella might have additive effects with photosensitizing drugs.
Chlorella has been reported to cause photosensitization. In five case reports, patients who had ingested chlorella exhibited swelling followed by erythematopurpuric lesions on sun-exposed areas of the body. Theoretically, concomitant use with photosensitizing drugs may exacerbate effects.
Warfarin (Coumadin)
Theoretically, chlorella might reduce the clinical effects of warfarin.
Chlorella contains significant amounts of vitamin K. There is at least one case report of warfarin therapy becoming sub-therapeutic after initiation of chlorella supplements.
Spirulina
Anticoagulant/Antiplatelet Drugs
Theoretically, spirulina blue-green algae might increase the risk of bleeding if used with other anticoagulant or antiplatelet drugs. However, this is unlikely.
Spirulina blue-green algae have shown antiplatelet and anticoagulant effects in vitro. However, one preliminary study in 24 patients receiving spirulina blue-green algae 2.3 grams daily for 2 weeks showed no effect on platelet activation or measures of clotting time.
Antidiabetes Drugs
Theoretically, taking blue-green algae with antidiabetes drugs might increase the risk of hypoglycemia.
Human research shows that spirulina blue-green algae can have hypoglycemic effects in patients with diabetes, at least some of whom were using antidiabetes drugs. However, blue-green algae does not seem to improve glycated hemoglobin (HbA1c) levels in patients with diabetes. A meta-analysis of animal studies also suggests that spirulina blue-green algae have hypoglycemic effects.
Immunosuppressants
Theoretically, concurrent use of blue-green algae might interfere with immunosuppressive therapy.
Blue-green algae have been shown to stimulate the immune system.
Sodium
Antihypertensive Drugs
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
High intake of dietary sodium can increase systolic and diastolic blood pressure. Also, high intake of sodium may necessitate increased use of antihypertensive medications to achieve blood pressure control in some patients, such as those with chronic kidney disease.
Corticosteroids
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Mineralocorticoids and some glucocorticoids (corticosteroids) cause sodium retention. This effect is dose-related and depends on mineralocorticoid potency. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Didanosine (Videx)
Concomitant use of didanosine with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia.
Didanosine formulations contain a significant amount of sodium.
Lithium
Altering dietary intake of sodium might alter the levels and clinical effects of lithium.
High sodium intake can reduce plasma concentrations of lithium by increasing lithium excretion. Reducing sodium intake can significantly increase plasma concentrations of lithium and cause lithium toxicity in patients being treated with lithium carbonate. Stabilizing sodium intake is shown to reduce the percentage of patients with lithium level fluctuations above 0.8 mEq/L. Patients taking lithium should avoid significant alterations in their dietary intake of sodium.
Sodium Phosphates
Theoretically, concomitant use of sodium phosphate with sodium supplements might increase the risk of hypernatremia.
Use of high doses (> 45 mL in 24 hours) of sodium phosphate, such as those used for bowel cleansing before surgery, can lead to serious electrolyte disturbances, including hypernatremia. The risk of hypernatremia is highest in the elderly and people with other risk factors for electrolyte disturbances.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related complications.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium supplements or high-sodium diets, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Tolvaptan (Samsca)
Theoretically, concomitant use of tolvaptan with sodium might increase the risk of hypernatremia.
Tolvaptan is a vasopressin receptor 2 antagonist that is used to increase sodium levels in patients with hyponatremia. Patients taking tolvaptan should use caution with the use of sodium salts such as sodium chloride.
Probiotic Culture Blend
Antibiotic Drugs
Theoretically, taking Lactobacillus acidophilus with antibiotic drugs might decrease the effectiveness of L. acidophilus.
L. acidophilus preparations usually contain live and active organisms. Therefore, simultaneously taking antibiotics might kill a significant number of the organisms. Tell patients to separate administration of antibiotics and L. acidophilus preparations by at least two hours.
Calcium
Ceftriaxone (Rocephin)
Co-administration of intravenous calcium and ceftriaxone can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys.
Avoid administering intravenous calcium in any form, such as parenteral nutrition or Lactated Ringers, within 48 hours of intravenous ceftriaxone. Case reports in neonates show that administering intravenous ceftriaxone and calcium can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys. In several cases, neonates have died as a result of this interaction. So far there are no reports in adults; however, there is still concern that this interaction might occur in adults.
Dolutegravir (Tivicay)
Calcium seems to reduce levels of dolutegravir.
Advise patients to take dolutegravir either 2 hours before or 6 hours after taking calcium supplements. Pharmacokinetic research suggests that taking calcium carbonate 1200 mg concomitantly with dolutegravir 50 mg reduces plasma levels of dolutegravir by almost 40%. Calcium appears to decrease levels of dolutegravir through chelation.
Elvitegravir (Vitekta)
Calcium seems to reduce levels of elvitegravir.
Advise patients to take elvitegravir either 2 hours before or 2 hours after taking calcium supplements. Pharmacokinetic research suggests that taking calcium along with elvitegravir can reduce blood levels of elvitegravir through chelation.
Aluminum
Calcium citrate might increase aluminum absorption and toxicity. Other types of calcium do not increase aluminum absorption.
Calcium citrate can increase the absorption of aluminum when taken with aluminum hydroxide. The increase in aluminum levels may become toxic, particularly in individuals with kidney disease. However, the effect of calcium citrate on aluminum absorption is due to the citrate anion rather than calcium cation. Calcium acetate does not appear to increase aluminum absorption.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Calcium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide and calcium can be taken together if taken with food. However, if taken on an empty stomach, bictegravir/emtricitabine/tenofovir alafenamide should not be taken with, or 2 hours after, calcium containing products.
Bisphosphonates
Calcium reduces the absorption of bisphosphonates.
Advise patients to take bisphosphonates at least 30 minutes before calcium, but preferably at a different time of day. Calcium supplements decrease absorption of bisphosphonates.
Calcipotriene (Dovonex)
Taking calcipotriene with calcium might increase the risk for hypercalcemia.
Calcipotriene is a vitamin D analog used topically for psoriasis. It can be absorbed in sufficient amounts to cause systemic effects, including hypercalcemia. Theoretically, combining calcipotriene with calcium supplements might increase the risk of hypercalcemia.
Digoxin (Lanoxin)
Using intravenous calcium with digoxin might increase the risk of fatal cardiac arrhythmias.
Hypercalcemia increases the risk of fatal cardiac arrhythmias with digoxin. However, one retrospective analysis of clinical data suggests that intravenous calcium does not increase the risk of dysrhythmias or mortality in patients receiving digoxin.
Diltiazem (Cardizem, Others)
Theoretically, calcium may reduce the therapeutic effects of diltiazem.
Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically, calcium might increase this risk of hypercalcemia and reduce the effectiveness of diltiazem.
Levothyroxine (Synthroid, Others)
Calcium seems to reduce the absorption and effectiveness of levothyroxine.
Advise patients to take levothyroxine and calcium supplements at least 4 hours apart. Calcium reduces levothyroxine absorption, probably by forming insoluble complexes. Calcium carbonate supplements reduce effectiveness of levothyroxine in patients with hypothyroidism.
Lithium
Theoretically, concomitant use of calcium and lithium may increase this risk of hypercalcemia.
Clinical research suggests that long-term use of lithium may cause hypercalcemia in 10% to 60% of patients. Theoretically, concomitant use of lithium and calcium supplements may further increase this risk.
Quinolone Antibiotics
Calcium seems to reduce the absorption of quinolone antibiotics.
Advise patients to take oral quinolones at least 2 hours before or 4-6 hours after calcium supplements or calcium-fortified foods. Taking calcium at the same time as oral quinolones can reduce quinolone absorption. Calcium binds to quinolones in the gut.
Raltegravir (Isentress)
Calcium may reduce levels of raltegravir.
Pharmacokinetic research shows that taking a single dose of calcium carbonate 3000 mg along with raltegravir 400 mg twice daily modestly decreases the mean area under the curve of raltegravir, but the decrease does not necessitate a dose adjustment of raltegravir. However, a case of elevated HIV-1 RNA levels and documented resistance to raltegravir has been reported for a patient taking calcium carbonate 1 gram three times daily plus vitamin D3 (cholecalciferol) 400 IU three times daily in combination with raltegravir 400 mg twice daily for 11 months. It is thought that calcium reduced raltegravir levels by chelation, leading to treatment failure.
Sotalol (Betapace)
Calcium seems to reduce the absorption of sotalol.
Advise patients to separate doses by at least 2 hours before or 4-6 hours after calcium. Calcium appears to reduce the absorption of sotalol, probably by forming insoluble complexes.
Tetracycline Antibiotics
Calcium seems to reduce the absorption of tetracycline antibiotics.
Advise patients to take oral tetracyclines at least 2 hours before, or 4-6 hours after calcium supplements. Taking calcium at the same time as oral tetracyclines can reduce tetracycline absorption. Calcium binds to tetracyclines in the gut.
Thiazide Diuretics
Taking calcium along with thiazides might increase the risk of hypercalcemia and renal failure.
Thiazides reduce calcium excretion by the kidneys. Using thiazides along with moderately large amounts of calcium carbonate increases the risk of milk-alkali syndrome (hypercalcemia, metabolic alkalosis, renal failure). Patients may need to have their serum calcium levels and/or parathyroid function monitored regularly.
Verapamil (Calan, Others)
Theoretically, calcium may reduce the therapeutic effects of verapamil.
Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically, use of calcium supplements may increase this risk of hypercalcemia and reduce the effectiveness of verapamil.
Calcium Channel Blockers
Intravenous calcium may decrease the effects of calcium channel blockers; oral calcium is unlikely to have this effect.
Intravenous calcium is used to decrease the effects of calcium channel blockers in the management of overdose. Intravenous calcium gluconate has been used before intravenous verapamil (Isoptin) to prevent or reduce the hypotensive effects without affecting the antiarrhythmic effects. But there is no evidence that dietary or supplemental calcium when taken orally interacts with calcium channel blockers.
Oat Grass
Antidiabetes Drugs
Theoretically, oats may have additive effects with antidiabetic agents and might increase the risk of hypoglycemia.
Consuming oats can decrease blood glucose in patients with diabetes. In those who require insulin, taking oats 100 grams daily for 2 days reduces the insulin dose required to achieve metabolic control.
Insulin
Concomitant use of oats and insulin might increase the risk of hypoglycemia.
In patients with insulin-dependent type 2 diabetes, taking oats 100 grams daily for 2 days reduces the insulin dose required to achieve metabolic control.
Potassium
Ace Inhibitors (Aceis)
Using ACEIs with high doses of potassium increases the risk of hyperkalemia.
ACEIs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Angiotensin Receptor Blockers (Arbs)
Using ARBs with high doses of potassium increases the risk of hyperkalemia.
ARBs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Potassium-Sparing Diuretics
Concomitant use increases the risk of hyperkalemia.
Using potassium-sparing diuretics with potassium supplements increases the risk of hyperkalemia.
Barley Grass
Triclabendazole (Egaten)
Theoretically, barley might decrease the clinical effects of triclabendazole.
Animal research suggests that a diet supplemented with barley can reduce the bioavailability of triclabendazole when taken concomitantly. This effect has not been shown in humans.
Pepitas
Lithium
Pumpkin might reduce excretion and increase levels of lithium.
Pumpkin is thought to have diuretic properties. Theoretically, this might reduce excretion and increase levels of lithium. The dose of lithium might need to be decreased.
Brand information
Manufacturer and brand details for 10 Billion Probiotic with Prebiotic Fiber Blend, from the product label.
Safrel
See all Safrel products- Name
- Safrel Pharmaceuticals LLC
- City
- Bridgewater
- State
- NJ
- ZipCode
- 08807
- Phone Number
- 1-844-384-3723
- Web Address
- www.safrel.com
10 Billion Probiotic with Prebiotic Fiber Blend by Safrel: Common Questions
Does 10 Billion Probiotic with Prebiotic Fiber Blend by Safrel interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take this while on antibiotics?
Does this product have side effects?
Is this safe to take while pregnant or breastfeeding?
What are the probiotics supposed to do?
What about the prebiotic fiber—what does it do?
Is this product free of fillers?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if 10 Billion Probiotic with Prebiotic Fiber Blend is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind 10 Billion Probiotic with Prebiotic Fiber Blend’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Sodium
Interacts with 205 drugsSodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets get more than enough—often too much—from...
Read the full Sodium monograph → Herb & supplement monographPotassium
Interacts with 62 drugsPotassium is an essential mineral your body needs for nerve signals, muscle function, and a steady heartbeat, and most people get enough from a balanced diet rich in fruits and vegetables. P...
Read the full Potassium monograph → Herb & supplement monographCalcium
Interacts with 168 drugsCalcium is an essential mineral your body needs for strong bones, nerve signaling, and muscle function, and supplements can help fill gaps when diet falls short. Most people do best getting...
Read the full Calcium monograph → Herb & supplement monographLactobacillus Acidophilus
Interacts with 182 drugsLactobacillus acidophilus is a 'friendly' bacterium used as a probiotic to support gut and vaginal health. It is generally well tolerated in healthy people, and there is reasonable evidence...
Read the full Lactobacillus Acidophilus monograph → Herb & supplement monographBifidobacterium Bifidum
Interacts with 182 drugsBifidobacterium bifidum is a 'friendly' bacteria (probiotic) that naturally lives in the human gut and is taken to support digestion and gut balance. Some evidence suggests probiotics may he...
Read the full Bifidobacterium Bifidum monograph → Herb & supplement monographSaccharomyces Boulardii
Interacts with 40 drugsSaccharomyces boulardii is a beneficial yeast used as a probiotic, with the strongest evidence for preventing and treating certain types of diarrhea, including antibiotic-associated diarrhea...
Read the full Saccharomyces Boulardii monograph → Herb & supplement monographLactobacillus Helveticus
Interacts with 182 drugsLactobacillus helveticus is a lactic acid bacterium used as a probiotic, often combined with other strains in mood, gut, and general wellness products. Early research is interesting—especial...
Read the full Lactobacillus Helveticus monograph → Herb & supplement monographBrewer's Yeast
Interacts with 136 drugsBrewer's yeast is a nutrient-rich fungus that provides B vitamins, protein, and minerals, and a related yeast product (S. boulardii) is used for some types of diarrhea. Most other health cla...
Read the full Brewer's Yeast monograph → Herb & supplement monographLactobacillus Delbrueckii
Interacts with 182 drugsLactobacillus delbrueckii is a 'friendly' bacterium used in food fermentation and sold as a probiotic, often as part of multi-strain products. It is generally considered safe for healthy peo...
Read the full Lactobacillus Delbrueckii monograph → Herb & supplement monographBlue-green Algae
Interacts with 327 drugsBlue-green algae are nutrient-rich aquatic microorganisms (such as spirulina and Klamath Lake algae) taken as a supplement for energy, nutrition, and general wellness. Evidence for most heal...
Read the full Blue-green Algae monograph → Herb & supplement monographChlorella
Interacts with 337 drugsChlorella is a nutrient-rich freshwater green algae taken as a supplement for general wellness, immune support, and 'detox.' Some small studies suggest possible benefits for cholesterol, blo...
Read the full Chlorella monograph → Herb & supplement monographRice Bran
Rice bran is the nutrient-rich outer layer of the rice grain and is a good source of fiber, healthy fats, and plant compounds. It is most studied for helping lower cholesterol, but for most...
Read the full Rice Bran monograph → Herb & supplement monographTurmeric
Interacts with 1,133 drugsTurmeric is a popular spice whose main active compounds, curcuminoids, are studied mostly for inflammation and joint pain. Some research is promising, but quality is mixed and curcumin is po...
Read the full Turmeric monograph → Herb & supplement monographBarley
Interacts with 1 drugBarley is a nutritious whole grain that is a good source of soluble fiber called beta-glucan, which has solid evidence for modestly lowering LDL ('bad') cholesterol when eaten regularly. It...
Read the full Barley monograph → Herb & supplement monographSweet Almond
Sweet almonds are a nutritious tree nut rich in healthy fats, fiber, protein, vitamin E, and minerals, and they are generally safe and healthy to eat as part of a balanced diet. Almond oil i...
Read the full Sweet Almond monograph → Herb & supplement monographAlfalfa
Interacts with 583 drugsAlfalfa is a nutrient-rich legume that people use for high cholesterol, menopause symptoms, and general wellness, but solid human evidence for most of these uses is limited. It is best avoid...
Read the full Alfalfa monograph → Herb & supplement monographGinger
Interacts with 1,007 drugsGinger is a widely used culinary spice with a long history in traditional medicine, and it has the strongest evidence for helping with nausea and vomiting, including from motion sickness, pr...
Read the full Ginger monograph → Herb & supplement monographOats
Interacts with 86 drugsOats are a well-studied whole grain whose soluble fiber (beta-glucan) can help lower cholesterol and support heart health when eaten regularly. As a food, oats are safe for most people, and...
Read the full Oats monograph → Herb & supplement monographPumpkin
Interacts with 1 drugPumpkin is a nutritious squash, and its seeds and seed oil are the parts most often used as supplements, mainly for urinary and prostate symptoms. The evidence for these uses is limited and...
Read the full Pumpkin monograph →Sources & How We Checked
10 Billion Probiotic with Prebiotic Fiber Blend's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 454 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Sodium 38 references
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Food and Drug Administration Science Background: Safety of Sodium Phosphates Oral Solution. September 17, 2001. Available at: http://www.fda.gov/cder/drug/safety/sodiumphospate.htm
- Coton T, Mallaret C, Coilliot C, Carre D, Guisset M. Severe acute ulcerated gastritis induced by salt. Presse Med 2009;38(3):499-500. PubMed
- Frings-Meuthen P, Buehlmeier J, Baecker N, et al. High sodium chloride intake exacerbates immobilization-induced bone resorption and protein losses. J Appl Physiol 2011;111(2):537-542. PubMed
- Frings-Meuthen P, Baecker N, Heer M. Low-grade metabolic acidosis may be the cause of sodium chloride-induced exaggerated bone resorption. J Bone Miner Res 2008;23(4):517-524. PubMed
- Alam S, Johnson AG. A meta-analysis of randomised controlled trials (RCT) among healthy normotensive and essential hypertensive elderly patients to determine the effect of high salt (NaCl) diet of blood pressure. J Hum Hypertens 1999;13(6):367-74.
- Boudville N, Ward S, Benaroia M, House AA. Increased sodium intake correlates with greater use of antihypertensive agents by subjects with chronic kidney disease. Am J Hypertens 2005;18(10):1300-5. PubMed
- Bennett WM. Drug interactions and consequences of sodium restriction. Am J Clin Nutr 1997;65(2 Suppl):678S-681S. PubMed
- Okusa MD, Crystal LJ. Clinical manifestations and management of acute lithium intoxication. Am J Med 1994;97(4):383-9. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary reference intakes for water, potassium, sodium, chloride, and sulfate. Washington, DC: National Academy Press, 2005. Available at: http://www.nap.edu/openbook.php?record_id=10925. DOI
- D'Elia L, Rossi G, Ippolito R, Cappuccio FP, Strazzullo P. Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clin Nutr 2012;31(4):489-98. PubMed
- Goldsmith SR. Hyponatremia in heart failure: time for a trial. J Card Fail 2013;19(6):398-400. PubMed
- Willocks L, Brettle R, Keen J, Valentine C, Pinching AJ. Formulations of didanosine (ddI) and salt overload. Lancet 1992;339(8786):190.
- Chen L, Zhang Z, Chen W, Whelton PK, Appel LJ. Lower Sodium Intake and Risk of Headaches: Results From the Trial of Nonpharmacologic Interventions in the Elderly. Am J Public Health. 2016;106(7):1270-5. PubMed
- Cook NR, Appel LJ, Whelton PK. Lower levels of sodium intake and reduced cardiovascular risk. Circulation. 2014;129(9):981-9. PubMed
- Cook NR, Appel LJ, Whelton PK. Sodium Intake and All-Cause Mortality Over 20 Years in the Trials of Hypertension Prevention. J Am Coll Cardiol. 2016;68(15):1609-1617. PubMed
- Mente A, O'Donnell M, Rangarajan S, et al. Associations of urinary sodium excretion with cardiovascular events in individuals with and without hypertension: a pooled analysis of data from four studies. Lancet. 2016;388(10043):465-75. PubMed
- Moosavian SP, Haghighatdoost F, Surkan PJ, Azadbakht L. Salt and obesity: a systematic review and meta-analysis of observational studies. Int J Food Sci Nutr. 2017;68(3):265-277. PubMed
- O'Donnell M, Mente A, Rangarajan S, et al. Urinary sodium and potassium excretion, mortality, and cardiovascular events. N Engl J Med. 2014;371(7):612-23. DOI
- Poggio R, Gutierrez L, Matta MG, Elorriaga N, Irazola V, Rubinstein A. Daily sodium consumption and CVD mortality in the general population: systematic review and meta-analysis of prospective studies. Public Health Nutr. 2015;18(4):695-704. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Mahtani KR, Heneghan C, Onakpoya I, et al. Reduced Salt Intake for Heart Failure: A Systematic Review. JAMA Intern Med. 2018 Dec 1;178(12):1693-1700. PubMed
- Yancy CW. Sodium Restriction in Heart Failure: Too Much Uncertainty-Do the Trials. JAMA Intern Med. 2018 Dec 1;178(12):1700-1701. PubMed
- He FJ, Campbell NRC, Ma Y, MacGregor GA, Cogswell ME, Cook NR. Errors in estimating usual sodium intake by the Kawasaki formula alter its relationship with mortality: implications for public health. Int J Epidemiol. 2018;47(6):1784-1795. PubMed
- Murthy K, Ondrey GJ, Malkani N, et al. THE EFFECTS OF HYPONATREMIA ON BONE DENSITY AND FRACTURES: A SYSTEMATIC REVIEW AND META-ANALYSIS. Endocr Pract. 2019;25(4):366-378. PubMed
- Messerli FH, Hofstetter L, Syrogiannouli L, et al. Sodium intake, life expectancy, and all-cause mortality. Eur Heart J 2021;42(21):2103-2112. PubMed
- Graudal NA, Hubeck-Graudal T, Jurgens G. Effects of low sodium diet versus high sodium diet on blood pressure, renin, aldosterone, catecholamines, cholesterol, and triglyceride. Cochrane Database Syst Rev 2020;12(12):CD004022. PubMed
- Giatti S, Santos RB, Aielo AN, et al. Association of sodium with obstructive sleep apnea. The ELSA-Brasil study. Ann Am Thorac Soc 2021;18(3):502-510. PubMed
- Nan X, Lu H, Wu J, et al. The interactive association between sodium intake, alcohol consumption and hypertension among elderly in northern China: a cross-sectional study. BMC Geriatr 2021;21(1):135. PubMed
- Kyozuka H, Fukusda T, Murata T, et al. Impact of preconception sodium intake on hypertensive disorders of pregnancy: The Japan Environment and Children's study. Pregnancy Hypertens 2021;23:66-72. PubMed
- Zhao L, Ogden CL, Yang Q, et al. Association of usual sodium intake with obesity among US children and adolescents, NHANES 2009-2016. Obesity (Silver Spring) 2021;29(3):587-594. PubMed
- Ma Y, He FJ, Sun Q, et al. 24-Hour urinary sodium and potassium excretion and cardiovascular risk. N Engl J Med 2022;386(3):252-263. PubMed
- Liu J, Yang X, Zhang P, et al. Association of urinary sodium excretion and left ventricular hypertrophy in people with type 2 diabetes mellitus: A cross-sectional study. Front Endocrinol (Lausanne) 2021;12:728493. PubMed
- Filippini T, Malavolti M, Whelton PK, Vinceti M. Sodium intake and risk of hypertension: A systematic review and dose-response meta-analysis of observational cohort studies. Curr Hypertens Rep 2022;24(5):133-144. PubMed
- Wang DD, Li Y, Nguyen XT, et al. Dietary sodium and potassium intake and risk of non-fatal cardiovascular diseases: The million veteran program. Nutrients 2022;14(5):1121. PubMed
- Kwak JH, Park CH, Eun CS, et al. The associations of dietary intake of high sodium and low zinc with gastric cancer mortality: A prospective cohort study in Korea. Nutr Cancer 2022;74(10):3501-3508. PubMed
- George S, Maiti R, Mishra BR, Jena M, Mohapatra D. Effect of regulated add-on sodium chloride intake on stabilization of serum lithium concentration in bipolar disorder: A randomized controlled trial. Bipolar Disord 2023;25(1):66-75. PubMed
- Zhou TL, Schütten MTJ, Kroon AA, et al. Urinary Sodium Excretion and Salt Intake Are Not Associated With Blood Pressure Variability in a White General Population. J Am Heart Assoc 2023;12(1):e026578. PubMed
Potassium 12 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Gennaro A. Remington: The Science and Practice of Pharmacy. 19th ed. Lippincott: Williams & Wilkins, 1996.
- Whelton PK, He J, Cutler JA, et al. Effects of oral potassium on blood pressure. Meta-analysis of randomized controlled clinical trials. JAMA 1997;277:1624-32. PubMed
- Phillips, C. O., Kashani, A., Ko, D. K., Francis, G., and Krumholz, H. M. Adverse effects of combination angiotensin II receptor blockers plus angiotensin-converting enzyme inhibitors for left ventricular dysfunction: a quantitative review of data from ra DOI
- Altieri, P. I., Herrero, C., Suero, R., and Ortiz, A. Bleeding duodenal ulcer in a patient taking slow-releasing potassium tablets. Bol.Asoc.Med P.R. 1977;69(8):276.
- Raf, L. E. Enteric-coated potassium chloride tablets and ulcer of the small intestine. Acta Chir Scand Suppl 1967;(374):1-87.
- Potassium chloride oral solution [package insert]. Allentown, PA: Lehigh Valley Technologies, Inc.; 2014.
- Potassium chloride injection [package insert]. Lake Forest, IL: Hospira Inc.; 2009.
- Patel RB, Tannenbaum S, Viana-Tejedor A, et al. Serum potassium levels, cardiac arrhythmias, and mortality following non-ST-elevation myocardial infarction or unstable angina: insights from MERLIN-TIMI 36. Eur Heart J Acute Cardiovasc Care 2017 Feb;6(1):1 PubMed
- Malta D, Arcand J, Ravindran A, Floras V, Allard JP, Newton GE. Adequate intake of potassium does not cause hyperkalemia in hypertensive individuals taking medications that antagonize the renin angiotensin aldosterone system. Am J Clin Nutr 2016 Oct;104(4 PubMed
- Keskin M, Kaya A, Tatlisu MA, et al. The effect of serum potassium level on in-hospital and long-term mortality in ST elevation myocardial infarction. Int J cardiol. 2016 Oct 15;221:505-10.
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
Calcium 62 references
- Shils M, Olson A, Shike M. Modern Nutrition in Health and Disease. 8th ed. Philadelphia, PA: Lea and Febiger, 1994.
- Hernandez-Avila M, Gonzalez-Cossio T, Hernandez-Avila JE, et al. Dietary calcium supplements to lower blood lead levels in lactating women: a randomized placebo-controlled trial. Epidemiology 2003;14:206-12.. PubMed
- Thys-Jacobs S, Ceccarelli S, Bierman A, et al. Calcium supplementation in premenstrual syndrome: a randomized crossover trial. J Gen Intern Med 1989;4:183-9. PubMed
- Maton PN, Burton ME. Antacids revisited: a review of their clinical pharmacology and recommended therapeutic use. Drugs 1999;57:855-70.
- Clemens JD, Feinstein AR. Calcium carbonate and constipation: a historical review of medical mythopoeia. Gastroenterology 1977;72:957-61. DOI
- Saunders D, Sillery J, Chapman R. Effect of calcium carbonate and aluminum hydroxide on human intestinal function. Dig Dis Sci 1988;33:409-13. PubMed
- Friedman PA, Bushinsky DA. Diuretic effects on calcium metabolism. Semin Nephrol 1999;19:551-6.
- Koo WK, Walters JC, Esterlitz J, et al. Maternal calcium supplementation and fetal bone mineralization. Obstet Gynecol 1999;94:577-82. DOI
- Raman L, Rajalakshmi K, Krishnamachari KAVR, et al. Effect of calcium supplementation to undernourished mothers during pregnancy on the bone density of the neonates. Am J Clin Nutr 1978; 31:466-9. DOI
- Murry JJ, Healy MD. Drug-mineral interactions: a new responsibility for the hospital dietician. J Am Diet Assoc 1991;91:66-73.
- Chan JM, Giovannucci E, Andersson SO, et al. Dairy products, calcium, phosphorous, vitamin D, and risk of prostate cancer. Cancer Causes Control 1998;9:559-66.
- Butner LE, Fulco PP, Feldman G, et al. Calcium carbonate-induced hypothyroidism. Ann Intern Med 2000:132:595. PubMed
- Schneyer CR. Calcium carbonate and reduction of levothyroxine efficacy. JAMA 1998;279:750. PubMed
- Moser LR, Smythe MA, Tisdale JE. The use of calcium salts in the prevention and management of verapamil-induced hypotension. Ann Pharmacother 2000;34:622-9. PubMed
- Singh N, Singh PN, Hershman JM. Effect of calcium carbonate on the absorption of levothyroxine. JAMA 2000;283:2822-5. PubMed
- Kahela P, Anttila M, Tikkanen R, Sundquist H. Effect of food, food constituents and fluid volume on the bioavailability of sotalol. Acta Pharmacol Toxicol (Copenh) 1979;44:7-12.. PubMed
- Pletz MW, Petzold P, Allen A, et al. Effect of calcium carbonate on bioavailability of orally administered gemifloxacin. Antimicrob Agents Chemother 2003;47:2158-60.. PubMed
- Bar-Or D, Yoel G. Calcium and calciferol antagonize effect of verapamil in atrial fibrillation. Br Med J 1981;282:1585-6.
- Decktor DL, Robinson M, Maton PN, et al. Effects of aluminum/magnesium hydroxide and calcium carbonate on esophageal and gastric pH in subjects with heartburn. Am J Ther 1995;2:546-52. PubMed
- Simoneau G. Absence of rebound effect with calcium carbonate. Eur J Drug Metab Pharmacokinet 1996;21:351-7. PubMed
- Peters ML, Leonard M, Licata AA. Role of alendronate and risedronate in preventing and treating osteoporosis. Cleve Clin J Med 2001;68:945-51. PubMed
- Bourke JF, Mumford R, Whittaker P, et al. The effects of topical calcipotriol on systemic calcium homeostasis in patients with chronic plaque psoriasis. J Am Acad Dermatol 1997;37:929-34.
- Gueguen L, Pointillart A. The bioavailability of dietary calcium. J Am Coll Nutr 2000;19:119s-136s. PubMed
- Vella A, Gerber TC, Hayes DL, Reeder GS. Digoxin, hypercalcaemia, and cardiac conduction. Postgrad Med J 1999;75:554-6. PubMed
- Bania TC, Blaufeux B, Hughes S, et al. Calcium and digoxin vs. calcium alone for severe verapamil toxicity. Acad Emerg Med 2000;7:1089-96. PubMed
- Tseng M, Breslow RA, Graubard BI, Ziegler RG. Dairy, calcium, and vitamin D intakes and prostate cancer risk in the National Health and Nutrition Examination Epidemiologic Follow-up Study cohort. Am J Clin Nutr 2005;81:1147-54. PubMed
- Weingarten MA, Zalmanovici A, Yaphe J. Dietary calcium supplementation for preventing colorectal cancer and adenomatous polyps. Cochrane Database Syst Rev 2004;(1):CD003548. PubMed
- Tavani A, Bertuccio P, Bosetti C, et al. Dietary intake of calcium, vitamin D, phosphorus and the risk of prostate cancer. Eur Urol 2005;48:27-33. PubMed
- Giovannucci E, Liu Y, Stampfer MJ, Willett WC. A prospective study of calcium intake and incident and fatal prostate cancer. Cancer Epidemiol Biomarkers Prev 2006;15:203-10. PubMed
- Rocephin (ceftriaxone) and calcium interaction. Pharmacist's Letter / Prescriber's Letter 2007;23(10):231005.
- Bolland MJ, Barber PA, Doughty RN, et al. Vascular events in healthy older women receiving calcium supplementation: randomised control trial. BMJ 2008;336:262-6.
- Bolland MJ, Avenell A, Baron JA, et al. Effect of calcium supplements on risk of myocardial infarction and cardiovascular events: meta-analysis. BMJ 2010;341:c3691. PubMed
- Calcium supplementation and vascular events. Pharmacist's Letter / Prescriber's Letter 2008;24(3):240306.
- Dietary reference intakes for calcium and vitamin D. Institute of Medicine, November 30, 2010. Available at: http://www.iom.edu/~/media/Files/Report%20Files/2010/Dietary-Reference-Intakes-for-Calcium-and-Vitamin-D/Vitamin%20D%20and%20Calcium%202010%20Repo
- Coburn JW, Mischel MG, Goodman WG, et al. Calcium citrate markedly enhances aluminum absorption from aluminum hydroxide. Am J Kidney Dis. 1991;17(6):708-11. PubMed
- Bradley JS, Wassel RT, Lee L, et al. Intravenous ceftriaxone and calcium in the neonate: assessing the risk for cardiopulmonary adverse events. Pediatrics. 2009;123(4):e609-13. PubMed
- Kays MB, Overholser BR, Mueller BA, et al. Effects of sevelamer hydrochloride and calcium acetate on the oral bioavailability of ciprofloxacin. Am J Kidney Dis. 2003;42(6):1253-9. PubMed
- Neuhofel, A. L., Wilton, J. H., Victory, J. M., Hejmanowsk, L. G., and Amsden, G. W. Lack of bioequivalence of ciprofloxacin when administered with calcium-fortified orange juice: a new twist on an old interaction. J Clin Pharmacol. 2002;42(4):461-466. DOI
- Dickinson, H. O., Nicolson, D. J., Cook, J. V., Campbell, F., Beyer, F. R., Ford, G. A., and Mason, J. Calcium supplementation for the management of primary hypertension in adults. Cochrane.Database.Syst.Rev. 2006;(2):CD004639. PubMed
- Jones, B. J. and Twomey, P. J. Requesting patterns for serum calcium concentration in patients on long-term lithium therapy. Int J Clin Pract. 2009;63(1):170-172. PubMed
- Levine, M., Nikkanen, H., and Pallin, D. J. The effects of intravenous calcium in patients with digoxin toxicity. J Emerg.Med. 2011;40(1):41-46. PubMed
- Castelo-Branco, C., Ciria-Recasens, M., Cancelo-Hidalgo, M. J., Palacios, S., Haya-Palazuelos, J., Carbonell-Abello, J., Blanch-Rubio, J., Martinez-Zapata, M. J., Manasanch, J., and Perez-Edo, L. Efficacy of ossein-hydroxyapatite complex compared with ca
- Li K, Kaaks R, Linseisen J, Rohrmann S. Associations of dietary calcium intake and calcium supplementation with myocardial infarction and stroke risk and overall cardiovascular mortality in the Heidelberg cohort of the European Prospective Investigation i
- Chung M, Tang AM, Fu Z. Calcium Intake and Cardiovascular Disease Risk: An Updated Systematic Review and Meta-analysis. Ann Intern Med. 2016 Oct 25. PubMed
- Nolan CR, Califano JR, Butzin CA. Influence of calcium acetate or calcium citrate on intestinal aluminum absorption. Kidney Int. 1990;38(5):937-41. PubMed
- Lewis JR, Radavelli-Bagatini S, Rejnmark L, et al. The effects of calcium supplementation on verified coronary heart disease hospitalization and death in postmenopausal women: a collaborative meta-analysis of randomized controlled trials. J Bone Miner Res PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Lappe J, Watson P, Travers-Gustafson D, Recker R, Garland C, Gorham E, Baggerly K, McDonnell SL. Effect of Vitamin D and Calcium Supplementation on Cancer Incidence in Older Women: A Randomized Clinical Trial. JAMA. 2017 Mar 28;317(12):1234-1243. PubMed
- Grove ML, Cook D. Calcium and heart attacks. Doesn't apply to most calcium prescriptions. BMJ. 2010;341:c5003. PubMed
- Insentress [package insert]. Whitehouse Station, NJ: Merck Sharp & Dohme Corp.; 2014.
- Roberts JL, Kiser JJ, Hindman JT, Meditz AL. Virologic failure with a raltegravir-containing antiretroviral regimen and concomitant calcium administration. Pharmacotherapy 2011;31(10):298e-302e. DOI
- Vitekta [package insert]. Foster City, CA: Gilead Sciences, Inc.; 2014.
- Storan ER, O'Gorman SM, Murphy A, Laing M. Case Report of Calciphylaxis Secondary to Calcium and Vitamin D<sub>3</sub> Supplementation. J Cutan Med Surg. 2017;21(2):162-163. DOI
- Jenkins DJA, Spence JD, Giovannucci EL, et al. Supplemental vitamins and minerals for CVD prevention and treatment. J Am Coll Cardiol 2018;71(22):2570-84. PubMed
- Borkenhagen JF, Connor EL, Stafstrom CE. Neonatal hypocalcemic seizures due to excessive maternal calcium ingestion. Pediatr Neurol 2013;48(6):469-71. PubMed
- WHO recommendations on antenatal care for a positive pregnancy experience. Geneva: World Health Organization; 2016 (http://www.who.int/reproductivehealth/publications/maternal_perinatal_health/ anc-positive-pregnancy-experience/en/).
- Aune D, Navarro Rosenblatt DA, Chan DS, et al. Dairy products, calcium, and prostate cancer risk: a systematic review and meta-analysis of cohort studies. Am J Clin Nutr. 2015;101(1):87-117. PubMed
- Lan T, Park Y, Colditz GA, et al. Adolescent dairy product and calcium intake in relation to later prostate cancer risk and mortality in the NIH-AARP Diet and Health Study. Cancer Causes Control. 2020;31(10):891-904. PubMed
- Zhang Y, Li Y, Liu J, et al. Association of Vitamin D or Calcium Supplementation with Cardiovascular Outcomes and Mortality: A Meta-Analysis with Trial Sequential Analysis. J Nutr Health Aging 2021;25(2):263-270. PubMed
- Myung SK, Kim HB, Lee YJ, Choi YJ, Oh SW. Calcium Supplements and Risk of Cardiovascular Disease: A Meta-Analysis of Clinical Trials. Nutrients 2021;13(2):368. PubMed
- Hetaimish B. Neonatal Calcinosis Cutis After Treatment of Hypocalcemia with Calcium Gluconate: A Report of 2 Cases. Am J Case Rep 2024;25:e943397. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Lactobacillus Acidophilus 15 references
- Pierce A. The American Pharmaceutical Association Practical Guide to Natural Medicines. New York: The Stonesong Press, 1999:19.
- Begtrup LM, de Muckadell OB, Kjeldsen J, Christensen RD, Jarbøl DE. Long-term treatment with probiotics in primary care patients with irritable bowel syndrome--a randomised, double-blind, placebo controlled trial. Scand J Gastroenterol 2013;48(10):1127-35 PubMed
- Chatterjee S, Kar P, Das T, Ray S, Gangulyt S, Rajendiran C, Mitra M. Randomised placebo-controlled double blind multicentric trial on efficacy and safety of Lactobacillus acidophilus LA-5 and Bifidobacterium BB-12 for prevention of antibiotic-associated
- Shavakhi A, Tabesh E, Yaghoutkar A, Hashemi H, Tabesh F, Khodadoostan M,Minakari M, Shavakhi S, Gholamrezaei A. The effects of multistrain probiotic compound on bismuth-containing quadruple therapy for Helicobacter pylori infection: a randomized placebo-c
- Karamali M, Dadkhah F, Sadrkhanlou M, et al. Effects of probiotic supplementation on glycaemic control and lipid profiles in gestational diabetes: a randomized, double-blind, placebo-controlled trial. Diabetes Metab 2016;42(4):234-41. PubMed
- Badehnoosh B, Karamali M, Zarrati M, et al. The effects of probiotic supplementation on biomarkers of inflammation, oxidative stress and pregnancy outcomes in gestational diabetes. J Matern Fetal Neonatal Med. 2018 May;31(9):1128-1136.
- Kumar S, Kumar R, Rohilla L, Jacob N, Yadav J, Sachdeva N. A high potency multi-strain probiotic improves glycemic control in children with new-onset type 1 diabetes mellitus: A randomized, double-blind, and placebo-controlled pilot study. Pediatr Diabete
- Shahriari A, Karimi E, Shahriari M, Aslani N, Khooshideh M, Arab A. The effect of probiotic supplementation on the risk of gestational diabetes mellitus among high-risk pregnant women: A parallel double-blind, randomized, placebo-controlled clinical trial PubMed
- Xiao SD, Zhang DZ, Lu H, et al. Multicenter, randomized, controlled trial of heat-killed Lactobacillus acidophilus LB in patients with chronic diarrhea. Adv Ther. 2003;20(5):253-60.
- Rossi F, Amadoro C, Gasperi M, Colavita G. Lactobacilli infection case reports in the last three years and safety implications. Nutrients. 2022;14(6):1178. PubMed
- Ozer M, Goksu SY, Shahverdiani A, Mustafa M. Lactobacillus acidophilus-induced endocarditis and associated splenic abscess. Case Rep Infect Dis 2020;2020:1382709.
- Sadrin S, Sennoune S, Gout B, et al. A 2-strain mixture of Lactobacillus acidophilus in the treatment of irritable bowel syndrome: A placebo-controlled randomized clinical trial. Dig Liver Dis 2020;52(5):534-540. PubMed
- Stoffer JN, Slingsby TJ, Giuliari GP. Lactobacillus acidophilus endophthalmitis after intravitreal bevacizumab injection requiring intraocular lens explantation. Can J Ophthalmol 2022;57(1):e21-e22. PubMed
- Cukovic-Cavka S, Likic R, Francetic I, Rustemovic N, Opacic M, Vucelic B. Lactobacillus acidophilus as a cause of liver abscess in a NOD2/CARD15-positive patient with Crohn's disease. Digestion 2006;73(2-3):107-10.
- Hui J, Ren Y, Wang Y, Han Q. Lactobacillus acidophilus endophthalmitis postcataract operation: A case report with a literature review. Ocul Immunol Inflamm 2023.
See these in context on the Lactobacillus Acidophilus monograph →
Bifidobacterium Bifidum 7 references
- Pierce A. The American Pharmaceutical Association Practical Guide to Natural Medicines. New York: The Stonesong Press, 1999:19.
- Xiao JZ, Takahashi S, Odamaki T, et al. Antibiotic susceptibility of bifidobacterial strains distributed in the Japanese market. Biosci Biotechnol Biochem. 2010;74(2):336-42. PubMed
- Rerksuppaphol S, Rerksuppaphol L. Randomized controlled trial of probiotics to reduce common cold in schoolchildren. Pediatr Int. 2012;54(5):682-7. PubMed
- Karamali M, Dadkhah F, Sadrkhanlou M, et al. Effects of probiotic supplementation on glycaemic control and lipid profiles in gestational diabetes: a randomized, double-blind, placebo-controlled trial. Diabetes Metab 2016;42(4):234-41. PubMed
- Badehnoosh B, Karamali M, Zarrati M, et al. The effects of probiotic supplementation on biomarkers of inflammation, oxidative stress and pregnancy outcomes in gestational diabetes. J Matern Fetal Neonatal Med. 2018 May;31(9):1128-1136.
- Pruccoli G, Silvestro E, Pace Napoleone C, Aidala E, Garazzino S, Scolfaro C. Are probiotics safe? Bifidobacterium bacteremia in a child with severe heart failure. Infez Med. 2019;27(2):175-178.
- Esaiassen E, Hjerde E, Cavanagh JP, Simonsen GS, Klingenberg C; Norwegian Study Group on Invasive Bifidobacterial Infections. Bifidobacterium bacteremia: Clinical characteristics and a genomic approach to assess pathogenicity. J Clin Microbiol. 2017;55(7) PubMed
See these in context on the Bifidobacterium Bifidum monograph →
Saccharomyces Boulardii 26 references
- Niault M, Thomas F, Prost J, et al. Fungemia due to Saccharomyces species in a patient treated with enteral Saccharomyces boulardii. Clin Infect Dis 1999;28:930.
- Pletinex M, Legein J, Vandenplas Y. Fungemia with Saccharomyces boulardii in a 1-year-old girl with protracted diarrhea. J Pediatr Gastroenterol Nutr 1995;21:113-5. DOI
- Fredenucci I, Chomarat M, Boucaud C, et al. Saccharomyces boulardii fungemia in a patient receiving ultra-levure therapy. Clin Infect Dis 1998;27:222-3.
- Elmer GW, McFarland LV, Surawicz CM, et al. Behaviour of Saccharomyces boulardii in recurrent Clostridium difficile disease patients. Aliment Pharmacol Ther 1999;13:1663-8.
- Lewis SJ, Freedman AR. Review article: the use of biotherapeutic agents in the prevention and treatment of gastrointestinal disease. Aliment Pharmacol Ther 1998;12:807-22. PubMed
- Cesaro S, Chinello P, Rossi L, Zanesco L. Saccharomyces cerevisiae fungemia in a neutropenic patient treated with Saccharomyces boulardii. Support Care Cancer 2000;8:504-5. PubMed
- Hennequin C, Thierry A, Richard GF, et al. Microsatellite typing as a new tool for identification of Saccharomyces cerevisiae strains. J Clin Microbiol 2001;39:551-9.
- Plein K, Hotz J. Therapeutic effects of Saccharomyces boulardii on mild residual symptoms in a stable phase of Crohn's disease with special respect to chronic diarrhea - a pilot study. Z Gastroenterol 1993;31:129-34.
- Borriello SP, Hammes WP, Holzapfel W, et al. Safety of probiotics that contain lactobacilli or bifidobacteria. Clin Infect Dis 2003;36:775-80. PubMed
- Marteau P, Seksik P. Tolerance of probiotics and prebiotics. J Clin Gastroenterol 2004;38:S67-9. PubMed
- Munoz P, Bouza E, Cuenca-Estrella M, et al. Saccharomyces cerevisiae fungemia: an emerging infectious disease. Clin Infect Dis 2005;40:1625-34. PubMed
- Lherm, T., Monet, C., Nougiere, B., Soulier, M., Larbi, D., Le Gall, C., Caen, D., and Malbrunot, C. Seven cases of fungemia with Saccharomyces boulardii in critically ill patients. Intensive Care Med 2002;28(6):797-801. PubMed
- Riquelme, A. J., Calvo, M. A., Guzman, A. M., Depix, M. S., Garcia, P., Perez, C., Arrese, M., and Labarca, J. A. Saccharomyces cerevisiae fungemia after Saccharomyces boulardii treatment in immunocompromised patients. J Clin.Gastroenterol. 2003;36(1):41- PubMed
- Cherifi, S., Robberecht, J., and Miendje, Y. Saccharomyces cerevisiae fungemia in an elderly patient with Clostridium difficile colitis. Acta Clin Belg. 2004;59(4):223-224. PubMed
- Ellouze O, Berthoud V, Mervant M, Parthiot JP, Girard C. Septic shock due to Sacccaromyces boulardii. Med Mal Infect. 2016;46(2):104-105.
- Appel-da-Silva MC, Narvaez GA, Perez LRR, Drehmer L, Lewgoy J. Saccharomyces cerevisiae var. boulardii fungemia following probiotic treatment. Med Mycol Case Rep. 2017;18:15-7. PubMed
- Atici S, Soysal A, Karadeniz Cerit K, et al. Catheter-related Saccharomyces cerevisiae Fungemia Following Saccharomyces boulardii Probiotic Treatment: In a child in intensive care unit and review of the literature. Med Mycol Case Rep. 2017;15:33-35. PubMed
- Martin IW, Tonner R, Trivedi J, et al. Saccharomyces boulardii probiotic-associated fungemia: questioning the safety of this preventive probiotic's use. Diagn Microbiol Infect Dis. 2017;87(3):286-8. PubMed
- Romanio MR, Coraine LA, Maielo VP, Abramczyc ML, Souza RL, Oliveira NF. Saccharomyces cerevisiae fungemia in a pediatric patient after treatment with probiotics. Rev Paul Pediatr 2017;35(3):361-4.
- Roy U, Jessani LG, Rudramurthy SM, et al. Seven cases of Saccharomyces fungaemia related to use of probiotics. Mycoses 2017;60(6):375-380.
- Romanio MR, Coraine LA, Maielo VP, Abramczyc ML, Souza RL, Oliveira NF. Saccharomyces cerevisiae fungemia in a pediatric patient after treatment with probiotics. Rev Paul Pediatr. 2017 Jul-Sep;35(3):361-364. doi: 10.1590/1984-0462/;2017;35;3;00014.
- Flatley EA, Wilde AM, Nailor MD. Saccharomyces boulardii for the prevention of hospital onset Clostridium difficile infection. J Gastrointestin Liver Dis. 2015;24(1):21-4. PubMed
- Ventoulis I, Sarmourli T, Amoiridou P, et al. Bloodstream infection by Saccharomyces cerevisiae in two COVID-19 patients after receiving supplementation of Saccharomyces in the ICU. J Fungi (Basel). 2020;6(3):98. PubMed
- Wombwell E, Bransteitter B, Gillen LR. Incidence of Saccharomyces cerevisiae fungemia in hospitalised patients administered Saccharomyces boulardii probiotic. Mycoses 2021;64(12):1521-1526.
- Rannikko J, Holmberg V, Karppelin M, et al. Fungemia and Other Fungal Infections Associated with Use of Saccharomyces boulardii Probiotic Supplements. Emerg Infect Dis 2021;27(8):2090-6.
- Awoyemi A, Mayerhofer C, Felix AS, et al. Rifaximin or Saccharomyces boulardii in heart failure with reduced ejection fraction: Results from the randomized GutHeart trial. EBioMedicine 2021;70:103511. PubMed
See these in context on the Saccharomyces Boulardii monograph →
Blue-green Algae 22 references
- Jensen GS, Ginsberg DJ, Huerta P, et al. Consumption of Aphanizomenon flos-aquae has rapid effects on the circulation and function of immune cells in humans. A novel approach to nutritional mobilization of the immune system. JANA 2000;2:50-6.
- Iwasa M, Yamamoto M, Tanaka Y, et al. Spirulina-associated hepatotoxicity. Am J Gastroenterol 2002;97:3212-13. PubMed
- Hayashi O, Katoh T, Okuwaki Y. Enhancement of antibody production in mice by dietary Spirulina platensis. J Nutr Sci Vitaminol (Tokyo) 1994;40:431-41.. PubMed
- Vitale S, Miller NR, Mejico LJ, et al. A randomized, placebo-controlled, crossover clinical trial of super blue-green algae in patients with essential blepharospasm or Meige syndrome. Am J Ophthalmol 2004;138:18-32. PubMed
- Mani UV, Desai S, Iyer U. Studies on the long-term effect of spirulina supplementation on serum lipid profile and glycated proteins in NIDDM patients. J Nutraceut 2000;2(3):25-32. DOI
- Chiu HF, Yang SP, Kuo YL, et al. Mechanisms involved in the antiplatelet effect of C-phycocyanin. Br J Nutr 2006;95:435-40. PubMed
- Hsiao G, Chou PH, Shen MY, et al. C-phycocyanin, a very potent and novel platelet aggregation inhibitor from Spirulina platensis. J Agric Food Chem 2005;53:7734-40.
- Katz M, Levine AA, Kol-Degani H, Kav-Venaki L. A compound herbal preparation (CHP) in the treatment of children with ADHD: a randomized controlled trial. J Atten Disord 2010;14:281-91. PubMed
- Madhyastha, H. K., Radha, K. S., Sugiki, M., Omura, S., and Maruyama, M. Purification of c-phycocyanin from Spirulina fusiformis and its effect on the induction of urokinase-type plasminogen activator from calf pulmonary endothelial cells. Phytomedicine PubMed
- Mazokopakis, E. E., Karefilakis, C. M., Tsartsalis, A. N., Milkas, A. N., and Ganotakis, E. S. Acute rhabdomyolysis caused by Spirulina (Arthrospira platensis). Phytomedicine. 2008;15(6-7):525-527. PubMed
- Halidou, Doudou M., Degbey, H., Daouda, H., Leveque, A., Donnen, P., Hennart, P., and Dramaix-Wilmet, M. [The effect of spiruline during nutritional rehabilitation: systematic review]. Rev.Epidemiol.Sante Publique 2008;56(6):425-431.
- Konno, T., Umeda, Y., Umeda, M., Kawachi, I., Oyake, M., and Fujita, N. [A case of inflammatory myopathy with widely skin rash following use of supplements containing Spirulina]. Rinsho Shinkeigaku 2011;51(5):330-333. PubMed
- Le TM, Knulst AC, Röckmann H. Anaphylaxis to Spirulina confirmed by skin prick test with ingredients of Spirulina tablets. Food Chem Toxicol 2014;74:309-10. PubMed
- Rzymski P, Niedzielski P, Kaczmarek N, Jurczak T, Klimaszyk P. The multidisciplinary approach to safety and toxicity assessment of microalgae-based food supplements following clinical cases of poisoning. Harmful Algae 2015;46:34-42. DOI
- Petrus M, Culerrier R, Campistron M, et al. First case report of anaphylaxis to spirulin: identification of phycocyanin as responsible allergen. Allergy 2010;65(7):924-5. PubMed
- Marles RJ, Barrett ML, Barnes J, et al. United States Pharmacopeia safety evaluation of spirulina. Crit Rev Food Sci Nutr 2011;51(7):593-604. PubMed
- Majdoub H, Ben Mansour M, Chaubet F, et al. Anticoagulant activity of a sulfated polysaccharide from the green alga Arthrospira platensis. Biochim Biophys Acta 2009;1790(10):1377-81. PubMed
- Cha BG, Kwak HW, Park AR, et al. Structural characteristics and biological performance of silk fibroin nanofiber containing microalgae spirulina extract. Biopolymers 2014;101(4):307-18. PubMed
- Jensen GS, Drapeau C, Lenninger M, Benson KF. Clinical safety of a high dose of phycocyanin-enriched aqueous extract from Arthrospira (Spirulina) platensis: results from a randomized, double-Blind, placebo-controlled study with a focus on anticoagulant ac
- Hamedifard Z, Milajerdi A, Reiner Z, Taghizadeh M, Kolahdooz F, Asemi Z. The effects of spirulina on glycemic control and serum lipoproteins in patients with metabolic syndrome and related disorders: A systematic review and meta-analysis of randomized con
- Moradi S, Zobeiri M, Feizi A, Clark CCT, Entezari MH. The effects of spirulina (Arthrospira platensis) supplementation on anthropometric indices, blood pressure, sleep quality, mental health, fatigue status and quality of life in patients with ulcerative
- Ghanbari F, Amerizadeh A, Behshood P, Moradi S, Asgary S. Effect of microalgae arthrospira on biomarkers of glycemic control and glucose metabolism: a systematic Review and meta-analysis. Curr Probl Cardiol 2022;47(10):100942. PubMed
Chlorella 13 references
- Peirce A. The American Pharmaceutical Association Practical Guide to Natural Medicines. New York, NY: William Morrow and Co., 1999.
- Ng TP, Tan WC, Lee YK. Occupational asthma in a pharmacist induced by chlorella, a unicellular algae preparation. Resp Med 1994;88:555-7. PubMed
- Jitsukawa K, Suizu R, Hidano A. Chlorella photosensitization. New phytophotodermatosis. Int J Dermatol 1984;23:263-8. PubMed
- Merchant RE, Carmack CA, Wise CM. Nutritional supplementation with Chlorella pyrenoidosa for patients with fibromyalgia syndrome: a pilot study. Phytother Res 2000;14:167-73.
- Merchant RE, Rice CD, Young HF. Dietary Chlorella pyrenoidosa for patients with malignant glioma: effects on immunocompetence, quality of life, and survival. Phytother Res 1990;4:220-31.
- Halperin SA, Smith B, Nolan C, et al. Safety and immunoenhancing effect of a Chlorella-derived dietary supplement in healthy adults undergoing influenza vaccination: randomized, double-blind, placebo-controlled trial. CMAJ 2003;169:111-7..
- Ohtake, T., Negishi, K., Okamoto, K., Oka, M., Maesato, K., Moriya, H., and Kobayashi, S. Manganese-induced Parkinsonism in a patient undergoing maintenance hemodialysis. Am J Kidney Dis 2005;46(4):749-753. PubMed
- Ng, T. P., Tan, W. C., and Lee, Y. K. Occupational asthma in a pharmacist induced by Chlorella, a unicellular algae preparation. Respir.Med. 1994;88(7):555-557. PubMed
- Ohkawa, S., Yoneda, Y., Ohsumi, Y., and Tabuchi, M. [Warfarin therapy and chlorella]. Rinsho Shinkeigaku 1995;35(7):806-807.
- Azocar J, Diaz A. Efficacy and safety of chlorella supplementation in adults with chronic hepatitis C virus infection. World J Gastroenterol 2013;19(7):1085-90. PubMed
- Panahi Y, Badeli R, Karami GR, Badeli Z, Sahebkar A. A randomized controlled trial of 6-week Chlorella vulgaris supplementation in patients with major depressive disorder. Complement Ther Med 2015;23(4):598-602. PubMed
- Nakano S, Takekoshi H, Nakano M. Chlorella pyrenoidosa supplementation reduces the risk of anemia, proteinuria and edema in pregnant women. Plant Foods Hum Nutr 2010;65(1):25-30. PubMed
- Yavasoglu I, Turgutkaya A, Bolaman Z. Chlorella-induced thrombocytopenia. Sao Paulo Med J 2018;136(6):602-3. PubMed
Lactobacillus Helveticus 2 references
- Pierce A. The American Pharmaceutical Association Practical Guide to Natural Medicines. New York: The Stonesong Press, 1999:19.
- Rossi F, Amadoro C, Gasperi M, Colavita G. Lactobacilli infection case reports in the last three years and safety implications. Nutrients. 2022;14(6):1178. PubMed
See these in context on the Lactobacillus Helveticus monograph →
Rice Bran 7 references
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Fujiwaki T, Furusho K. The effects of rice bran broth bathing in patients with atopic dermatitis. Acta Paediatr Jpn 1992;34:505-10.
- Uenotsuchi T, Satoh E, Kiryu H, Yano Y. Pyemotes dermatitis caused by indirect contact with husk rice. Br J Dermatol 2000;143:680-2. DOI
- Satoh R, Tsuge I, Tokuda R, Teshima R. Analysis of the distribution of rice allergens in brown rice grains and of the allergenicity of products containing rice bran. Food Chem. 2019;276:761-767. PubMed
- Togashi Y, Inomata N, Suzuki A, Hakuta A, Aihara M. Pediatric case with rice bran allergy induced by epicutaneous sensitization in a family rice shop. Allergol Int. 2019;68(1):117-118. PubMed
- So WKW, Chan JYW, Law BMH, et al. Effects of a Rice Bran Dietary Intervention on the Composition of the Intestinal Microbiota of Adults with a High Risk of Colorectal Cancer: A Pilot Randomised-Controlled Trial. Nutrients 2021;13(2):526. PubMed
- Haneda Y, Kadowaki S, Furui M, Taketani T. A pediatric case of food-dependent exercise-induced anaphylaxis due to rice bran. Asia Pac Allergy 2021;11(1):e4. PubMed
Brewer's Yeast 6 references
- Blumenthal M, ed. The Complete German Commission E Monographs: Therapeutic Guide to Herbal Medicines. Trans. S. Klein. Boston, MA: American Botanical Council, 1998.
- Lewis SJ, Freedman AR. Review article: the use of biotherapeutic agents in the prevention and treatment of gastrointestinal disease. Aliment Pharmacol Ther 1998;12:807-22. PubMed
- Bahijiri, S. M., Mira, S. A., Mufti, A. M., and Ajabnoor, M. A. The effects of inorganic chromium and brewer's yeast supplementation on glucose tolerance, serum lipids and drug dosage in individuals with type 2 diabetes. Saudi.Med.J. 2000;21(9):831-837. DOI
- Schrauzer, G. N. and de, Vroey E. Effects of nutritional lithium supplementation on mood. A placebo-controlled study with former drug users. Biol.Trace Elem.Res. 1994;40(1):89-101. PubMed
- Gayathri R, Aruna T, Malar S, Shilpa B, Dhanasekar KR. Efficacy of Saccharomyces cerevisiae CNCM I-3856 as an add-on therapy for irritable bowel syndrome. Int J Colorectal Dis. 2020;35(1):139-145. PubMed
- Mourey F, Decherf A, Jeanne JF, et al. Saccharomyces cerevisiae I-3856 in irritable bowel syndrome with predominant constipation. World J Gastroenterol 2022;28(22):2509-2522.
Turmeric 102 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Sharma RA, McLelland HR, Hill KA, et al. Pharmacodynamic and pharmacokinetic study of oral Curcuma extract in patients with colorectal cancer. Clin Cancer Res 2001;7:1894-900..
- Shah BH, Nawaz Z, Pertani SA. Inhibitory effect of curcumin, a food spice from turmeric, on platelet-activating factor- and arachidonic acid-mediated platelet aggregation through inhibition of thromboxane formation and Ca2+ signaling. Biochem Pharmacol 1 PubMed
- Hata M, Sasaki E, Ota M, et al . Allergic contact dermatitis from curcumin (turmeric). Contact Dermatitis 1997;36:107-8. PubMed
- Kuttan R, Sudheeran PC, Josph CD. Turmeric and curcumin as topical agents in cancer therapy. Tumori 1987;73:29-31.. PubMed
- Thapliyal R, Deshpande SS, Maru GB. Mechanism(s) of turmeric-mediated protective effects against benzo(a)pyrene-derived DNA adducts. Cancer Lett 2002;175:79-88. PubMed
- Lee SW, Nah SS, Byon JS, et al. Transient complete atrioventricular block associated with curcumin intake. Int J Cardiol 2011;150:e50-2. PubMed
- Kuptniratsaikul V, Thanakhumtorn S, Chinswangwatanakul P, et al. Efficacy and safety of Curcuma domestica extracts in patients with knee osteoarthritis. J Altern Complement Med 2009;15:891-7.
- Carroll RE, Benya RV, Turgeon DK, et al. Phase IIa clinical trial of curcumin for the prevention of colorectal neoplasia. Cancer Prev Res (Phila) 2011;4:354-64. PubMed
- Junyaprasert, V. B., Soonthornchareonnon, N., Thongpraditchote, S., Murakami, T., and Takano, M. Inhibitory effect of Thai plant extracts on P-glycoprotein mediated efflux. Phytother.Res 2006;20(1):79-81. PubMed
- Ampasavate, C., Sotanaphun, U., Phattanawasin, P., and Piyapolrungroj, N. Effects of Curcuma spp. on P-glycoprotein function. Phytomedicine. 2010;17(7):506-512. PubMed
- Hou, X. L., Takahashi, K., Tanaka, K., Tougou, K., Qiu, F., Komatsu, K., Takahashi, K., and Azuma, J. Curcuma drugs and curcumin regulate the expression and function of P-gp in Caco-2 cells in completely opposite ways. Int.J Pharm 6-24-2008;358(1-2):224-2 PubMed
- Choi, B. H., Kim, C. G., Lim, Y., Shin, S. Y., and Lee, Y. H. Curcumin down-regulates the multidrug-resistance mdr1b gene by inhibiting the PI3K/Akt/NF kappa B pathway. Cancer Lett. 1-18-2008;259(1):111-118.
- Zhang, W., Tan, T. M., and Lim, L. Y. Impact of curcumin-induced changes in P-glycoprotein and CYP3A expression on the pharmacokinetics of peroral celiprolol and midazolam in rats. Drug Metab Dispos. 2007;35(1):110-115. PubMed
- Limtrakul, P., Chearwae, W., Shukla, S., Phisalphong, C., and Ambudkar, S. V. Modulation of function of three ABC drug transporters, P-glycoprotein (ABCB1), mitoxantrone resistance protein (ABCG2) and multidrug resistance protein 1 (ABCC1) by tetrahydrocu
- Holland, M. L., Panetta, J. A., Hoskins, J. M., Bebawy, M., Roufogalis, B. D., Allen, J. D., and Arnold, J. C. The effects of cannabinoids on P-glycoprotein transport and expression in multidrug resistant cells. Biochem.Pharmacol 4-14-2006;71(8):1146-1154 PubMed
- Tang, X. Q., Bi, H., Feng, J. Q., and Cao, J. G. Effect of curcumin on multidrug resistance in resistant human gastric carcinoma cell line SGC7901/VCR. Acta Pharmacol Sin. 2005;26(8):1009-1016. PubMed
- Nabekura, T., Kamiyama, S., and Kitagawa, S. Effects of dietary chemopreventive phytochemicals on P-glycoprotein function. Biochem.Biophys.Res Commun. 2-18-2005;327(3):866-870. PubMed
- Romiti, N., Tongiani, R., Cervelli, F., and Chieli, E. Effects of curcumin on P-glycoprotein in primary cultures of rat hepatocytes. Life Sci. 1998;62(25):2349-2358. PubMed
- Yue, G. G., Cheng, S. W., Yu, H., Xu, Z. S., Lee, J. K., Hon, P. M., Lee, M. Y., Kennelly, E. J., Deng, G., Yeung, S. K., Cassileth, B. R., Fung, K. P., Leung, P. C., and Lau, C. B. The role of turmerones on curcumin transportation and P-glycoprotein acti
- Shenouda, N. S., Zhou, C., Browning, J. D., Ansell, P. J., Sakla, M. S., Lubahn, D. B., and MacDonald, R. S. Phytoestrogens in common herbs regulate prostate cancer cell growth in vitro. Nutr.Cancer 2004;49(2):200-208. PubMed
- Appiah-Opong, R., Commandeur, J. N., Vugt-Lussenburg, B., and Vermeulen, N. P. Inhibition of human recombinant cytochrome P450s by curcumin and curcumin decomposition products. Toxicology 6-3-2007;235(1-2):83-91. PubMed
- Hou, X. L., Takahashi, K., Kinoshita, N., Qiu, F., Tanaka, K., Komatsu, K., Takahashi, K., and Azuma, J. Possible inhibitory mechanism of Curcuma drugs on CYP3A4 in 1alpha,25 dihydroxyvitamin D3 treated Caco-2 cells. Int.J Pharm 6-7-2007;337(1-2):169-177.
- Valentine, S. P., Le Nedelec, M. J., Menzies, A. R., Scandlyn, M. J., Goodin, M. G., and Rosengren, R. J. Curcumin modulates drug metabolizing enzymes in the female Swiss Webster mouse. Life Sci. 4-11-2006;78(20):2391-2398. PubMed
- Price, R. J., Scott, M. P., Giddings, A. M., Walters, D. G., Stierum, R. H., Meredith, C., and Lake, B. G. Effect of butylated hydroxytoluene, curcumin, propyl gallate and thiabendazole on cytochrome P450 forms in cultured human hepatocytes. Xenobiotica 2 PubMed
- Ganta, S., Devalapally, H., and Amiji, M. Curcumin enhances oral bioavailability and anti-tumor therapeutic efficacy of paclitaxel upon administration in nanoemulsion formulation. J Pharm Sci 2010;99(11):4630-4641. PubMed
- Lamb, S. R. and Wilkinson, S. M. Contact allergy to tetrahydrocurcumin. Contact Dermatitis 2003;48(4):227. PubMed
- Joshi, J., Ghaisas, S., Vaidya, A., Vaidya, R., Kamat, D. V., Bhagwat, A. N., and Bhide, S. Early human safety study of turmeric oil (Curcuma longa oil) administered orally in healthy volunteers. J Assoc.Physicians India 2003;51:1055-1060.
- Mahesh, T., Balasubashini, M. S., and Menon, V. P. Effect of photo-irradiated curcumin treatment against oxidative stress in streptozotocin-induced diabetic rats. J Med.Food 2005;8(2):251-255. PubMed
- Thompson, D. A. and Tan, B. B. Tetrahydracurcumin-related allergic contact dermatitis. Contact Dermatitis 2006;55(4):254-255. PubMed
- Patumraj, S., Wongeakin, N., Sridulyakul, P., Jariyapongskul, A., Futrakul, N., and Bunnag, S. Combined effects of curcumin and vitamin C to protect endothelial dysfunction in the iris tissue of STZ-induced diabetic rats. Clin Hemorheol.Microcirc. 2006;3
- Liddle, M., Hull, C., Liu, C., and Powell, D. Contact urticaria from curcumin. Dermatitis 2006;17(4):196-197. PubMed
- Juan, H., Terhaag, B., Cong, Z., Bi-Kui, Z., Rong-Hua, Z., Feng, W., Fen-Li, S., Juan, S., Jing, T., and Wen-Xing, P. Unexpected effect of concomitantly administered curcumin on the pharmacokinetics of talinolol in healthy Chinese volunteers. Eur.J Clin PubMed
- Murugan, P. and Pari, L. Influence of tetrahydrocurcumin on erythrocyte membrane bound enzymes and antioxidant status in experimental type 2 diabetic rats. J Ethnopharmacol. 9-25-2007;113(3):479-486. PubMed
- Seo, K. I., Choi, M. S., Jung, U. J., Kim, H. J., Yeo, J., Jeon, S. M., and Lee, M. K. Effect of curcumin supplementation on blood glucose, plasma insulin, and glucose homeostasis related enzyme activities in diabetic db/db mice. Mol.Nutr.Food Res 2008;5
- Weisberg, S. P., Leibel, R., and Tortoriello, D. V. Dietary curcumin significantly improves obesity-associated inflammation and diabetes in mouse models of diabesity. Endocrinology 2008;149(7):3549-3558. PubMed
- Jain, S. K., Rains, J., Croad, J., Larson, B., and Jones, K. Curcumin supplementation lowers TNF-alpha, IL-6, IL-8, and MCP-1 secretion in high glucose-treated cultured monocytes and blood levels of TNF-alpha, IL-6, MCP-1, glucose, and glycosylated hemog
- Yu, Y., Hu, S. K., and Yan, H. [The study of insulin resistance and leptin resistance on the model of simplicity obesity rats by curcumin]. Zhonghua Yu Fang Yi.Xue.Za Zhi. 2008;42(11):818-822.
- Pavithra, B. H., Prakash, N., and Jayakumar, K. Modification of pharmacokinetics of norfloxacin following oral administration of curcumin in rabbits. J Vet.Sci. 2009;10(4):293-297. PubMed
- Yan, Y. D., Kim, D. H., Sung, J. H., Yong, C. S., and Choi, H. G. Enhanced oral bioavailability of docetaxel in rats by four consecutive days of pre-treatment with curcumin. Int J Pharm 10-31-2010;399(1-2):116-120. PubMed
- Epelbaum, R., Schaffer, M., Vizel, B., Badmaev, V., and Bar-Sela, G. Curcumin and gemcitabine in patients with advanced pancreatic cancer. Nutr Cancer 2010;62(8):1137-1141. PubMed
- Madkor, H. R., Mansour, S. W., and Ramadan, G. Modulatory effects of garlic, ginger, turmeric and their mixture on hyperglycaemia, dyslipidaemia and oxidative stress in streptozotocin-nicotinamide diabetic rats. Br J Nutr 2011;105(8):1210-1217. PubMed
- Pungcharoenkul, K. and Thongnopnua, P. Effect of different curcuminoid supplement dosages on total in vivo antioxidant capacity and cholesterol levels of healthy human subjects. Phytother Res 2011;25(11):1721-1726.
- Kusuhara, H., Furuie, H., Inano, A., Sunagawa, A., Yamada, S., Wu, C., Fukizawa, S., Morimoto, N., Ieiri, I., Morishita, M., Sumita, K., Mayahara, H., Fujita, T., Maeda, K., and Sugiyama, Y. Pharmacokinetic interaction study of sulphasalazine in healthy
- Mohammadi, A., Sahebkar, A., Iranshahi, M., Amini, M., Khojasteh, R., Ghayour-Mobarhan, M., and Ferns, G. A. Effects of supplementation with curcuminoids on dyslipidemia in obese patients: a randomized crossover trial. Phytother Res 2013;27(3):374-379. PubMed
- Chuengsamarn, S., Rattanamongkolgul, S., Luechapudiporn, R., Phisalaphong, C., and Jirawatnotai, S. Curcumin extract for prevention of type 2 diabetes. Diabetes Care 2012;35(11):2121-2127. PubMed
- Goh, C. L. and Ng, S. K. Allergic contact dermatitis to Curcuma longa (turmeric). Contact Dermatitis 1987;17(3):186. PubMed
- Srivastava, R., Puri, V., Srimal, R. C., and Dhawan, B. N. Effect of curcumin on platelet aggregation and vascular prostacyclin synthesis. Arzneimittelforschung. 1986;36(4):715-717.
- Srinivasan, M. Effect of curcumin on blood sugar as seen in a diabetic subject. Indian J Med Sci 1972;26(4):269-270.
- Srivastava, K. C., Bordia, A., and Verma, S. K. Curcumin, a major component of food spice turmeric (Curcuma longa) inhibits aggregation and alters eicosanoid metabolism in human blood platelets. Prostaglandins Leukot.Essent.Fatty Acids 1995;52(4):223-227 PubMed
- Oetari, S., Sudibyo, M., Commandeur, J. N., Samhoedi, R., and Vermeulen, N. P. Effects of curcumin on cytochrome P450 and glutathione S-transferase activities in rat liver. Biochem Pharmacol 1-12-1996;51(1):39-45. PubMed
- Kiec-Swierczynska, M. and Krecisz, B. Occupational allergic contact dermatitis due to curcumin food colour in a pasta factory worker. Contact Dermatitis 1998;39(1):30-31. PubMed
- Van Dau N, Ngoc Ham N, Huy Khac D, and et al. The effects of a traditional drug, tumeric (Curcuma longa), and placebo on the healing of duodenal ulcer. Phytomed 1998;5(1):29-34.
- Daveluy A, Géniaux H, Thibaud L, Mallaret M, Miremont-Salamé G, Haramburu F. Probable interaction between an oral vitamin K antagonist and turmeric (Curcuma longa). Therapie. 2014 Nov-Dec;69(6):519-20. PubMed
- Kuptniratsaikul V, Dajpratham P, Taechaarpornkul W, Buntragulpoontawee M, Lukkanapichonchut P, Chootip C, Saengsuwan J, Tantayakom K, Laongpech S. Efficacy and safety of Curcuma domestica extracts compared with ibuprofen in patients with knee osteoarthrit
- Madhu K, Chanda K, Saji MJ. Safety and efficacy of Curcuma longa extract in the treatment of painful knee osteoarthritis: a randomized placebo-controlled trial. Inflammopharmacology 2013;21(2):129-36. PubMed
- Mali AM, Behal R, Gilda SS. Comparative evaluation of 0.1% turmeric mouthwash with 0.2% chlorhexidine gluconate in prevention of plaque and gingivitis: A clinical and microbiological study. J Indian Soc Periodontol 2012;16(3):386-91. PubMed
- Sanmukhani J, Satodia V, Trivedi J, Patel T, Tiwari D, Panchal B, Goel A, Tripathi CB. Efficacy and safety of curcumin in major depressive disorder: a randomized controlled trial. Phytother Res 2014;28(4):579-85. PubMed
- Nayeri A, Wu S, Adams E, et al. Acute Calcineurin Inhibitor Nephrotoxicity Secondary to Turmeric Intake: A Case Report. Transplant Proc. 2017;49(1):198-200. PubMed
- Mitchell TM. Correspondence re: Somasundaram et al., Dietary curcumin inhibits chemotherapy-induced apoptosis in models of human breast cancer. Cancer Res. 2003;63(16):5165-6; author reply 5166-7.
- Somasundaram S, Edmund NA, Moore DT, Small GW, Shi YY, Orlowski RZ. Dietary curcumin inhibits chemotherapy-induced apoptosis in models of human breast cancer. Cancer Res. 2002;62(13):3868-75.
- Haroyan A, Mukuchyan V, Mkrtchyan N, et al. Efficacy and safety of curcumin and its combination with boswellic acid in osteoarthritis: a comparative, randomized, double-blind, placebo-controlled study. BMC Complement Altern Med. 2018;18(1):7. PubMed
- Al-Karawi D, Al Mamoori DA, Tayyar Y. The role of curcumin administration in patients with major depressive disorder: Mini meta-analysis of clinical trials. Phytother Res. 2016;30(2):175-83. PubMed
- Neerati P, Devde R, Gangi AK. Evaluation of the effect of curcumin capsules on glyburide therapy in patients with type-2 diabetes mellitus. Phytother Res. 2014;28(12):1796-800. PubMed
- Simental-Mendía LE, Pirro M, Gotto AM Jr, et al. Lipid-modifying activity of curcuminoids: A systematic review and meta-analysis of randomized controlled trials. Crit Rev Food Sci Nutr. 2017:1-10. PubMed
- Fung FY, Wong WH, Ang SK, et al. A randomized, double-blind, placebo- controlled study on the anti-haemostatic effects of Curcuma longa, Angelica sinensis and Panax ginseng. Phytomedicine. 2017;32:88-96. PubMed
- Small GW, Siddarth P, Li Z, et al. Memory and brain amyloid and tau effects of a bioavailable form of curcumin in non-demented adults: A double-blind, placebo-controlled 18-month trial. Am J Geriatr Psychiatry. 2018;26(3):266-277.
- Cruz-Correa M, Hylind LM, Marrero JH, et al. Efficacy and safety of curcumin in treatment of intestinal adenomas in patients with familial adenomatous polyposis. Gastroenterology. 2018 May 23. Pii:S0016-5085(18)34564-5. [Epub ahead of print] PubMed
- Rahmani S, Asgary S, Askari G, et al. Treatment of non-alcoholic fatty liver disease with curcumin: a randomized placebo-controlled trial. Phytother Res. 2016 Sep;30(9):1540-8. PubMed
- Lopez-Villafuerte L, CLores KH. Contact dermatitis caused by turmeric in a massage oil. Contact Dermatitis. 2016 Jul;75(1):52-3. PubMed
- Lukefahr AL, McEvoy S, Alfafara C, Funk JL. Drug-induced autoimmune hepatitis associated with turmeric dietary supplement use. BMJ Case Rep. 2018. pii: bcr-2018-224611. PubMed
- Medsafe Safety Communication- Turmeric/Curcumin Interaction with Warfarin. April 30, 2018. Accessed at: https://medsafe.govt.nz/safety/EWS/2018/Turmeric.asp.
- Imam Z, Khasawneh M, Jomaa D, Iftikhar H, Sayedahmad Z. Drug induced liver injury attributed to a curcumin supplement. Case Rep Gastrointest Med 2019 Oct 20;2019:6029403. doi: 10.1155/2019/6029403. PubMed
- Chand S, Hair C, Beswick L. A rare case of turmeric-induced hepatotoxicity. Intern Med J. 2020;50(2):258-259. PubMed
- Jiang N, Zhang M, Meng X, Sun B. Effects of Curcumin on the Pharmacokinetics of Amlodipine in Rats and Its Potential Mechanism. Pharm Biol. 2020;58(1):465-468. PubMed
- Lee BS, Bhatia T, Chaya CT, Wen R, Taira MT, Lim BS. Autoimmune Hepatitis Associated With Turmeric Consumption. ACG Case Rep J. 2020;7(3):e00320. PubMed
- Lombardi N, Crescioli G, Maggini V, et al. Acute liver injury following turmeric use in Tuscany: an analysis of the Italian Phytovigilance database and systematic review of case reports. Br J Clin Pharmacol. 2020. PubMed
- Suhail FK, Masood U, Sharma A, John S, Dhamoon A. Turmeric supplement induced hepatotoxicity: a rare complication of a poorly regulated substance. Clin Toxicol (Phila). 2020;58(3):216-217. PubMed
- Nakagawa Y, Mukai S, Yamada S, et al. The efficacy and safety of highly-bioavailable curcumin for treating knee osteoarthritis: a 6-month open-labeled prospective study. Clin Med Insights Arthritis Musculoskelet Disord. 2020;13:1179544120948471. PubMed
- Shafabakhsh R, Asemi Z, Reiner Z, Soleimani A, Aghadavod E, Bahmani F. The effects of nano-curcumin on metabolic status in patients with diabetes on hemodialysis, a randomized, double blind, placebo-controlled trial. Iran J Kidney Dis. 2020;14(4):290-9.
- Allegri P, Rosa R, Masala A, et al. Clinical effectiveness of a new oral curcumin formulation in acute non-infectious uveitic macular edema: a 12-month observational study. Eur Rev Med Pharmacol Sci 2022;26(1):46-53.
- Tsai IC, Hsu CW, Chang CH, Tseng PT, Chang KV. The effect of curcumin differs on individual cognitive domains across different patient populations: A systematic review and meta-analysis. Pharmaceuticals (Basel) 2021;14(12):1235. PubMed
- Alam MA, Bin Jardan YA, Raish M, Al-Mohizea AM, Ahad A, Al-Jenoobi FI. Herb-drug interaction: Pharmacokinetics and pharmacodynamics of anti-hypertensive drug amlodipine besylate in presence of lepidium sativum and curcuma longa. Xenobiotica 2022;1-9.
- Sohal A, Alhankawi D, Sandhu S, Chintanaboina J. Turmeric-induced hepatotoxicity: Report of 2 cases. Int Med Case Rep J 2021;14:849-852. PubMed
- Hussaarts KGAM, Hurkmans DP, Oomen-de Hoop E, et al. Impact of curcumin (with or without piperine) on the pharmacokinetics of tamoxifen. Cancers (Basel). 2019;11(3):403. PubMed
- Kalluru H, Mallayasamy SR, Kondaveeti SS, Chandrasekhar V, Kalachaveedu M. Effect of turmeric supplementation on the pharmacokinetics of paclitaxel in breast cancer patients: A study with population pharmacokinetics approach. Phytother Res 2022;36(4):1761 PubMed
- 109288 Halegoua-DeMarzio D, Navarro V, Ahmad J, et al. Liver injury associated with turmeric-A growing problem: Ten cases from the drug-induced liver injury network [DILIN]. Am J Med. 2022:S0002-9343(22)00740-9. PubMed
- Arzallus T, Izagirre A, Castiella A, Torrente S, Garmendia M, Zapata EM. Drug induced autoimmune hepatitis after turmeric intake. Gastroenterol Hepatol 2023. PubMed
- Gilad O, Rosner G, Ivancovsky-Wajcman D, et al. Efficacy of wholistic turmeric supplement on adenomatous polyps in patients with familial adenomatous polyposis-A randomized, double-blinded, placebo-controlled study. Genes (Basel) 2022;13(12):2182. PubMed
- Ahad A, Raish M, Abdelrahman IA, et al. Changes in pharmacokinetics and pharmacodynamics of losartan in experimental diseased rats treated with Curcuma longa and Lepidium sativum. Pharmaceuticals (Basel) 2022;16(1):33. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
- Kou H, Huang L, Jin M, He Q, Zhang R, Ma J. Effect of curcumin on rheumatoid arthritis: a systematic review and meta-analysis. Front Immunol 2023;14:1121655. PubMed
- Qiu L, Gao C, Wang H, et al. Effects of dietary polyphenol curcumin supplementation on metabolic, inflammatory, and oxidative stress indices in patients with metabolic syndrome: a systematic review and meta-analysis of randomized controlled trials. Front PubMed
- Sato T, Yagi A, Yamauchi M, et al. The use of an antioxidant enables accurate evaluation of the interaction of curcumin on organic anion-transporting polypeptides 4C1 by preventing auto-oxidation. Int J Mol Sci 2024;25(2):991. PubMed
- Washington O, Robinson E, Simh D, et al. Oxalate nephropathy and chronic turmeric supplementation: a case report. J Bras Nefrol 2024;46(1):99-106. PubMed
- Munshi R, Karande-Patil S, Kumbhar D, Deshmukh A, Hingorani L. A randomized, controlled, comparative, proof-of-concept study to evaluate the efficacy and safety of Nisha-Amalaki capsules in prediabetic patients for preventing progression to diabetes. J Ay PubMed
- Sharifi Razavi A, Mohajerani F, Niksolat F, Karimi N. Efficacy of topical curcumin on mild to moderate carpal tunnel syndrome: a randomized double-blind, placebo-controlled clinical trial. Pain Med 2024;25(5):327-333. PubMed
- Yaikwawong M, Jansarikit L, Jirawatnotai S, Chuengsamarn S. Curcumin Reduces Depression in Obese Patients with Type 2 Diabetes: A Randomized Controlled Trial. Nutrients 2024;16(15):2414. PubMed
- Tehrani SD, Hosseini A, Shahzamani M, et al. Evaluation of the effectiveness of curcumin and piperine co-supplementation on inflammatory factors, cardiac biomarkers, atrial fibrillation, and clinical outcomes after coronary artery bypass graft surgery. Cl PubMed
- Yaikwawong M, Jansarikit L, Jirawatnotai S, Chuengsamarn S. The Effect of Curcumin on Reducing Atherogenic Risks in Obese Patients with Type 2 Diabetes: A Randomized Controlled Trial. Nutrients 2024;16(15):2441. PubMed
- Dibaei M, Hosseini A, Lavasani H, Kiani-Dehkordi B, Rouini M. Assessment of metabolic interaction between curcumin and tramadol using the isolated perfused rat liver. Heliyon 2024;10(15):e35070. PubMed
Barley 15 references
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
- Fernandez-Anaya S, Crespo JF, Rodriguez JR, et al. Beer anaphylaxis. J Allergy Clin Immunol 1999;103:959-60.
- Lembo A, Camilleri M. Chronic constipation. N Engl J Med 2003;349:1360-8. . PubMed
- Ferre, I., Giraldez, F. J., Alvarez-Bujidos, M. L., and Mantecon, A. R. Influence of barley supplement on plasma concentration of triclabendazole metabolites in sheep. Vet.Rec. 11-22-1997;141(21):549-551. PubMed
- Curioni, A., Santucci, B., Cristaudo, A., Canistraci, C., Pietravalle, M., Simonato, B., and Giannattasio, M. Urticaria from beer: an immediate hypersensitivity reaction due to a 10- kDa protein derived from barley. Clin Exp Allergy 1999;29(3):407-413. PubMed
- Fernandez-Anaya, S., Crespo, J. F., Rodriguez, J. R., Daroca, P., Carmona, E., Herraez, L., and Lopez-Rubio, A. Beer anaphylaxis. J Allergy Clin Immunol. 1999;103(5 Pt 1):959-960.
- Cronin, E. Contact dermatitis from barley dust. Contact Dermatitis 1979;5(3):196. PubMed
- Block, G., Tse, K. S., Kijek, K., Chan, H., and Chan-Yeung, M. Baker's asthma. Studies of the cross-antigenicity between different cereal grains. Clin Allergy 1984;14(2):177-185.
- van Ketel, W. G. Immediate type allergy to malt in beer. Contact Dermatitis 1980;6(4):297-298. PubMed
- Ellis, H. J., Doyle, A. P., Day, P., Wieser, H., and Ciclitira, P. J. Demonstration of the presence of coeliac-activating gliadin-like epitopes in malted barley. Int Arch Allergy Immunol. 1994;104(3):308-310. PubMed
- Vidal, C. and Gonzalez-Quintela, A. Food-induced and occupational asthma due to barley flour. Ann Allergy Asthma Immunol. 1995;75(2):121-124.
- Gutgesell, C. and Fuchs, T. Contact urticaria from beer. Contact Dermatitis 1995;33(6):436-437. PubMed
- Baker, P. G. and Read, A. E. Oats and barley toxicity in coeliac patients. Postgrad.Med J 1976;52(607):264-268. PubMed
- Nakase, M., Usui, Y., Alvarez-Nakase, A. M., Adachi, T., Urisu, A., Nakamura, R., Aoki, N., Kitajima, K., and Matsuda, T. Cereal allergens: rice-seed allergens with structural similarity to wheat and barley allergens. Allergy 1998;53(46 Suppl):55-57. PubMed
- Pereira, F., Rafael, M., and Lacerda, M. H. Contact dermatitis from barley. Contact Dermatitis 1998;39(5):261-262. PubMed
Sweet Almond 4 references
- Motaharifard MS, Effatpanah M, Karimi M, et al. Effect of sweet almond syrup versus methylphenidate in children with ADHD: A randomized triple-blind clinical trial. Complement Ther Clin Pract. 2019;36:170-175. PubMed
- Simon D, Nobbe S, Nägeli M, et al. Short- and long-term effects of two emollients on itching and skin restoration in xerotic eczema. Dermatol Ther. 2018;31(6):e12692. PubMed
- Food and Drug Administration. Food Allergen Labeling and Consumer Protection Act of 2004 (FALCPA); Public Law 108-282, Title II. Accessed on May 19, 2021. Available at: https://www.fda.gov/food/food-allergensgluten-free-guidance-documents-regulatory-infor
- Salama M, Tebben PJ, Al Nofal A. An infant developing hypercalcemia and hypophosphatemia due to the use of exclusively almond milk. J Pediatr Endocrinol Metab 2024;37(4):375-379. PubMed
Alfalfa 32 references
- Newall CA, Anderson LA, Philpson JD. Herbal Medicine: A Guide for Healthcare Professionals. London, UK: The Pharmaceutical Press, 1996.
- The Review of Natural Products by Facts and Comparisons. St. Louis, MO: Wolters Kluwer Co., 1999.
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- Kurzer MS, Xu X. Dietary phytoestrogens. Annu Rev Nutr 1997;17:353-81. PubMed
- Farber JM, Carter AO, Varughese PV, et al. Listeriosis traced to the consumption of alfalfa tablets and soft cheese [Letter to the Editor]. N Engl J Med 1990;322:338. PubMed
- Molgaard J, von Schenck H, Olsson AG. Alfalfa seeds lower low density lipoprotein cholesterol and apolipoprotein B concentrations in patients with type II hyperlipoproteinemia. Atherosclerosis 1987;65:173-9. PubMed
- Light TD, Light JA. Acute renal transplant rejection possibly related to herbal medications. Am J Transplant 2003;3:1608-9. PubMed
- Prete PE. The mechanism of action of L-canavanine in inducing autoimmune phenomena. Arthritis Rheum 1985;28:1198-200. PubMed
- Alcocer-Varela J, Iglesias A, Llorente L, Alarcon-Segovia D. Effects of L-canavanine on T cells may explain the induction of systemic lupus erythematosus by alfalfa. Arthritis Rheum 1985;28:52-7. PubMed
- Roberts JL, Hayashi JA. Exacerbation of SLE associated with alfalfa ingestion. N Engl J Med 1983;308:1361. DOI
- Feingold, R. M. Should we fear "health foods"? Arch Intern Med 7-12-1999;159(13):1502. PubMed
- Taormina, P. J., Beuchat, L. R., and Slutsker, L. Infections associated with eating seed sprouts: an international concern. Emerg.Infect.Dis 1999;5(5):626-634. PubMed
- Backer, H. D., Mohle-Boetani, J. C., Werner, S. B., Abbott, S. L., Farrar, J., and Vugia, D. J. High incidence of extra-intestinal infections in a Salmonella Havana outbreak associated with alfalfa sprouts. Public Health Rep. 2000;115(4):339-345. PubMed
- Mohle-Boetani J, Werner B, Polumbo M, and et al. From the Centers for Disease Control and Prevention. Alfalfa sprouts-- Arizona, California, Colorado, and New Mexico, February-April, 2001. JAMA 2-6-2002;287(5):581-582.
- Howard, M. B. and Hutcheson, S. W. Growth dynamics of Salmonella enterica strains on alfalfa sprouts and in waste seed irrigation water. Appl.Environ.Microbiol. 2003;69(1):548-553.
- Winthrop, K. L., Palumbo, M. S., Farrar, J. A., Mohle-Boetani, J. C., Abbott, S., Beatty, M. E., Inami, G., and Werner, S. B. Alfalfa sprouts and Salmonella Kottbus infection: a multistate outbreak following inadequate seed disinfection with heat and chl
- Strapp, C. M., Shearer, A. E., and Joerger, R. D. Survey of retail alfalfa sprouts and mushrooms for the presence of Escherichia coil O157:H7, Salmonella, and Listeria with BAX, and evaluation of this polymerase chain reaction-based system with experimen
- Akaogi, J., Barker, T., Kuroda, Y., Nacionales, D. C., Yamasaki, Y., Stevens, B. R., Reeves, W. H., and Satoh, M. Role of non-protein amino acid L-canavanine in autoimmunity. Autoimmun.Rev 2006;5(6):429-435. PubMed
- Burden and causes of foodborne disease in Australia: Annual report of the OzFoodNet network, 2005. Commun.Dis Intell. 2006;30(3):278-300.
- Shemesh, M., Lindner, H. R., and Ayalon, N. Affinity of rabbit uterine oestradiol receptor for phyto-oestrogens and its use in a competitive protein-binding radioassay for plasma coumestrol. J Reprod.Fertil. 1972;29(1):1-9. PubMed
- Elakovich, S. D. and Hampton, J. M. Analysis of coumestrol, a phytoestrogen, in alfalfa tablets sold for human consumption. J Agric.Food Chem. 1984;32(1):173-175. PubMed
- Malinow, M. R., Bardana, E. J., Jr., Pirofsky, B., Craig, S., and McLaughlin, P. Systemic lupus erythematosus-like syndrome in monkeys fed alfalfa sprouts: role of a nonprotein amino acid. Science 4-23-1982;216(4544):415-417. PubMed
- Malinow, M. R., McLaughlin, P., and Stafford, C. Alfalfa seeds: effects on cholesterol metabolism. Experientia 5-15-1980;36(5):562-564. PubMed
- Farnsworth, N. R. Alfalfa pills and autoimmune diseases. Am J Clin Nutr. 1995;62(5):1026-1028. DOI
- Herbert, V. and Kasdan, T. S. Alfalfa, vitamin E, and autoimmune disorders. Am J Clin Nutr 1994;60(4):639-640.
- Mahon, B. E., Ponka, A., Hall, W. N., Komatsu, K., Dietrich, S. E., Siitonen, A., Cage, G., Hayes, P. S., Lambert-Fair, M. A., Bean, N. H., Griffin, P. M., and Slutsker, L. An international outbreak of Salmonella infections caused by alfalfa sprouts grow
- Gray, A. M. and Flatt, P. R. Pancreatic and extra-pancreatic effects of the traditional anti- diabetic plant, Medicago sativa (lucerne). Br J Nutr. 1997;78(2):325-334.
- Van Beneden, C. A., Keene, W. E., Strang, R. A., Werker, D. H., King, A. S., Mahon, B., Hedberg, K., Bell, A., Kelly, M. T., Balan, V. K., Mac Kenzie, W. R., and Fleming, D. Multinational outbreak of Salmonella enterica serotype Newport infections due to
- Rubenstein AH, Levin NW, and Elliott GA. Manganese-induced hypoglycemia. Lancet 1962;1348-1351.
- Kaufman W. Alfalfa seed dermatitis. JAMA 1954;155(12):1058-1059. PubMed
- Ponka A, Andersson Y, Siitonen A, and et al. Salmonella in alfalfa sprouts. Lancet 1995;345:462-463. PubMed
- Puschner B, Chen X, Read D, Affolter VK. Alfalfa hay induced primary photosensitization in horses. Vet J. 2016 May;211:32-8. PubMed
Ginger 64 references
- Fischer-Rasmussen W, Kjaer SK, Dahl C, Asping U. Ginger treatment of hyperemesis gravidarum. Eur J Obstet Gynecol Reprod Biol 1991;38:19-24. PubMed
- Jewell D, Young G. Interventions for nausea and vomiting in early pregnancy. Cochrane Database Syst Rev 2000;(2):CD000145. PubMed
- Vutyavanich T, Kraisarin T, Ruangsri R. Ginger for nausea and vomiting in pregnancy: randomized, double-masked, placebo-controlled trial. Obstet Gynecol 2001;97:577-82. DOI
- Backon J. Ginger in preventing nausea and vomiting of pregnancy; a caveat due to its thromboxane synthetase activity and effect on testosterone binding. Eur J Obstet Gynecol Reprod Biol 1991;42:163-4. PubMed
- Srivastava KC. Effect of onion and ginger consumption on platelet thromboxane production in humans. Prostaglandins Leukot Essent Fatty Acids 1989;35:183-5. PubMed
- Stewart JJ, Wood MJ, Wood CD, Mims ME. Effects of ginger on motion sickness susceptibility and gastric function. Pharmacology 1991;42:111-20. PubMed
- Smith C, Crowther C, Willson K, et al. A randomized controlled trial of ginger to treat nausea and vomiting in pregnancy. Obstet Gynecol 2004;103:639-45. PubMed
- Portnoi G, Chng LA, Karimi-Tabesh L, et al. Prospective comparative study of the safety and effectiveness of ginger for the treatment of nausea and vomiting in pregnancy. Am J Obstet Gynecol 2003;189:1374-7.. PubMed
- Wigler I, Grotto I, Caspi D, Yaron M. The effects of Zintona EC (a ginger extract) on symptomatic gonarthritis. Osteoarthritis Cartilage 2003;11:783-9. PubMed
- Ghayur MN, Gilani AH. Ginger lowers blood pressure through blockade of voltage-dependent calcium channels. J Cardiovasc Pharmacol 2005;45:74-80. PubMed
- Thomson M, Al-Qattan KK, Al-Sawan SM, et al. The use of ginger (Zingiber officinale Rosc.) as a potential anti-inflammatory and antithrombotic agent. Prostaglandins Leukot Essent Fatty Acids 2002;67:475-8. PubMed
- Kanerva L, Estlander T, Jolanki R. Occupational allergic contact dermatitis from spices. Contact Dermatitis 1996;35:157-62. PubMed
- Akhani SP, Vishwakarma SL, Goyal RK. Anti-diabetic activity of Zingiber officinale in streptozotocin-induced type I diabetic rats. J Pharm Pharmacol 2004;56:101-5.
- Kruth P, Brosi E, Fux R, et al. Ginger-associated overanticoagulation by phenprocoumon. Ann Pharmacother 2004;38:257-60. PubMed
- Jiang X, Williams KM, Liauw WS, et al. Effect of ginkgo and ginger on the pharmacokinetics and pharmacodynamics of warfarin in healthy subjects. Br J Clin Pharmacol 2005;59:425-32. PubMed
- Borrelli F, Capasso R, Aviello G, et al. Effectiveness and safety of ginger in the treatment of pregnancy-induced nausea and vomiting. Obstet Gynecol 2005;105:849-56. PubMed
- Smith C, Crowther C, Wilson K et al. A randomized controlled trial of ginger to treat nausea and vomiting in pregnancy. Obstet Gynecol 2004;103:639-45. PubMed
- Jiang X, Blair EY, McLachlan AJ. Investigation of the effects of herbal medicines on warfarin response in healthy subjects: a population pharmacokinetic-pharmacodynamic modeling approach. J Clin Pharmacol 2006;46:1370-8. PubMed
- Chittumma P, Kaewkiattikun K, Wiriyasiriwach B. Comparison of the effectiveness of ginger and vitamin B6 for treatment of nausea and vomiting in early pregnancy: a randomized double-blind controlled trial. J Med Assoc Thai 2007;90:15-20.
- Ozgoli G, Goli M, Moattar F. Comparison of effects of ginger, mefenamic acid, and ibuprofen on pain in women with primary dysmenorrhea. J Altern Complement Med 2009;15:129-32. PubMed
- Black CD, Herring MP, Hurley DJ, O'Connor PJ. Ginger (Zingiber officinale) reduces muscle pain caused by eccentric exercise. J Pain 2010;11:894-903. PubMed
- Heitmann K, Nordeng H, Holst L. Safety of ginger use in pregnancy: results from a large population-based cohort study. Eur J Clin Pharmacol 2012 Jun 17. PubMed
- Ryan JL, Heckler CE, Roscoe JA, et al. Ginger (Zingiber officinale) reduces acute chemotherapy-induced nausea: a URCC CCOP study of 576 patients. Support Care Cancer. 2012;20:1479-89. PubMed
- Backon J. Ginger as an antiemetic: possible side effects due to its thromboxane synthetase activity. Anaesthesia. 1991;46(8):705-6.. PubMed
- Abebe W. Herbal medication: potential for adverse interactions with analgesic drugs. J Clin Pharm Ther. 2002;27:391-401. PubMed
- Argento A, Tiraferri E, Marzaloni M. [Oral anticoagulants and medicinal plants. An emerging interaction]. Ann Ital Med Int. 2000;15:139-43.
- Young HY, Liao JC, Chang YS, et al. Synergistic effect of ginger and nifedipine on human platelet aggregation: a study in hypertensive patients and normal volunteers. Am J Chin Med. 2006;34:545-51. PubMed
- Greenway FL, Liu Z, Martin CK, et al. Safety and efficacy of NT, an herbal supplement, in treating human obesity. Int J Obes (Lond). 2006;30:1737-41. PubMed
- Shalansky S, Lynd L, Richardson K, et al. Risk of warfarin-related bleeding events and supratherapeutic international normalized ratios associated with complementary and alternative medicine: a longitudinal analysis. Pharmacotherapy. 2007;27:1237-47. PubMed
- Lesho EP, Saullo L, Udvari-Nagy S. A 76-year-old woman with erratic anticoagulation. Cleve Clin J Med. 2004;71:651-6. PubMed
- Okonta JM, Uboh M, Obonga WO. Herb-Drug Interaction: A Case Study of Effect of Ginger on the Pharmacokinetic of Metronidazole in Rabbit. Indian Journal of Pharmaceutical Sciences (India) 2008;70(230):232. PubMed
- Chiang HM, Chao PD, Hsiu SL, et al. Ginger significantly decreased the oral bioavailability of cyclosporine in rats. Am J Chin Med. 2006;34:845-55. PubMed
- Bhandari U, Kanojia R, Pillai KK. Effect of ethanolic extract of Zingiber officinale on dyslipidaemia in diabetic rats. J Ethnopharmacol. 2005;97:227-30. PubMed
- Ojewole JA. Analgesic, antiinflammatory and hypoglycaemic effects of ethanol extract of Zingiber officinale (Roscoe) rhizomes (Zingiberaceae) in mice and rats. Phytother Res. 2006;20:764-72.
- Al-Amin ZM, Thomson M, Al-Qattan KK, et al. Anti-diabetic and hypolipidaemic properties of ginger (Zingiber officinale) in streptozotocin-induced diabetic rats. Br J Nutr. 2006;96:660-6.
- Islam MS, Choi H. Comparative effects of dietary ginger (Zingiber officinale) and garlic (Allium sativum) investigated in a type 2 diabetes model of rats. J Med Food. 2008;11:152-9.
- Cady RK, Goldstein J, Nett R, et al. A double-blind placebo-controlled pilot study of sublingual feverfew and ginger (LipiGesic M) in the treatment of migraine. Headache 2011;51:1078-86.
- Futrell, J. M. and Rietschel, R. L. Spice allergy evaluated by results of patch tests. Cutis 1993;52(5):288-290.
- Sripramote, M. and Lekhyananda, N. A randomized comparison of ginger and vitamin B6 in the treatment of nausea and vomiting of pregnancy. J Med Assoc.Thai. 2003;86(9):846-853.
- Lohsiriwat, S., Rukkiat, M., Chaikomin, R., and Leelakusolvong, S. Effect of ginger on lower esophageal sphincter pressure. J.Med.Assoc.Thai. 2010;93(3):366-372.
- Liu, P. H. and Ho, H. L. Ginger and drug bezoar induced small bowel obstruction. J R.Coll.Surg.Edinb. 1983;28(6):397-398.
- Maghbooli M, Golipour F, Moghimi Esfandabadi A, Yousefi M. Comparison between the efficacy of ginger and sumatriptan in the ablative treatment of the common migraine. Phytother Res 2014;28(3):412-5. PubMed
- Mahluji S, Attari VE, Mobasseri M, Payahoo L, Ostadrahimi A, Golzari SE. Effects of ginger (Zingiber officinale) on plasma glucose level, HbA1c and insulin sensitivity in type 2 diabetic patients. Int J Food Sci Nutr 2013;64(6):682-6.
- Mozaffari-Khosravi H, Talaei B, Jalali BA, Najarzadeh A, Mozayan MR. The effect of ginger powder supplementation on insulin resistance and glycemic indices in patients with type 2 diabetes: a randomized, double-blind, placebo-controlled trial. Complement PubMed
- Paramdeep G. Efficacy and tolerability of ginger (Zingiber officinale) in patients of osteoarthritis of knee. Indian J Physiol Pharmacol 2013;57(2):177-83.
- Rahnama P, Montazeri A, Huseini HF, Kianbakht S, Naseri M. Effect of Zingiber officinale R. rhizomes (ginger) on pain relief in primary dysmenorrhea: a placebo randomized trial. BMC Complement Altern Med 2012;12:92. PubMed
- Viljoen E, Visser J, Koen N, Musekiwa A. A systematic review and meta-analysis of the effect and safety of ginger in the treatment of pregnancy-associated nausea and vomiting. Nutr J 2014;13:20. PubMed
- Bartels EM, Folmer VN, Bliddal H, et al. Efficacy and safety of ginger in osteoarthritis patients: a meta-analysis of randomized placebo-controlled trials. Osteoarthritis Cartilage. 2015;23(1):13-21. PubMed
- Choi JS, Han JY, Ahn HK, et al. Assessment of fetal and neonatal outcomes in the offspring of women who had been treated with dried ginger (Zingiberis rhizoma siccus) for a variety of illnesses during pregnancy. J Obstet Gynaecol. 2015;35(2):125-30.
- Marx W, McKavanagh D, McCarthy AL, Bird R, Ried K, Chan A, Isenring L. The effect of ginger (Zingiber officinale) on platelet aggregation: A systematic literature review. PLoS One. 2015;10(10):e0141119. PubMed
- Crichton M, Marshall S, Marx W, McCarthy AL, Isenring E. Efficacy of ginger (Zingiber officinale) in ameliorating chemotherapy-induced nausea and vomiting and chemotherapy-related outcomes: A systematic review update and meta-analysis. J Acad Nutr Diet. 2 PubMed
- Martins LB, Rodrigues AMDS, Monteze NM, et al. Double-blind placebo-controlled randomized clinical trial of ginger (Zingiber officinale Rosc.) in the prophylactic treatment of migraine. Cephalalgia. 2020;40(1):88-95.
- Martins LB, Rodrigues AMDS, Rodrigues DF, Dos Santos LC, Teixeira AL, Ferreira AVM. Double-blind placebo-controlled randomized clinical trial of ginger (Zingiber officinale Rosc.) addition in migraine acute treatment. Cephalalgia. 2019;39(1):68-76.
- Ahad A, Raish M, Bin Jardan YA, Alam MA, Al-Mohizea AM, Al-Jenoobi FI. Effect of Hibiscus sabdariffa and Zingiber officinale on the antihypertensive activity and pharmacokinetic of losartan in hypertensive rats. Xenobiotica. 2020:1-11.
- Okuhira H, Nakatani Y, Furukawa F, Kanazawa N. Anaphylaxis to ginger induced by herbal medicine. Allergol Int. 2020;69(1):159-160. PubMed
- Yamprasert R, Chanvimalueng W, Mukkasombut N, Itharat A. Ginger extract versus Loratadine in the treatment of allergic rhinitis: a randomized controlled trial. BMC Complement Med Ther. 2020;20(1):116. PubMed
- Ebrahimzadeh A, Ebrahimzadeh A, Mirghazanfari SM, Hazrati E, Hadi S, Milajerdi A. The effect of ginger supplementation on metabolic profiles in patients with type 2 diabetes mellitus: a systematic review and meta-analysis of randomized controlled trials. PubMed
- Alam MA, Bin Jardan YA, Alzenaidy B, et al. Effect of Hibiscus sabdariffa and Zingiber officinale on pharmacokinetics and pharmacodynamics of amlodipine. J Pharm Pharmacol 2021;73(9):1151-60.
- Akbarzadeh E, Heydari M, Atarzadeh F, Jaladat AM. Chronic dysuria following ginger (Zingiber officinale) use: a case report. Galen Med J 2018;7:e1086. DOI
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Rostamkhani H, Veisi P, Niknafs B, Jafarabadi MA, Ghoreishi Z. The effect of zingiber officinale on prooxidant-antioxidant balance and glycemic control in diabetic patients with ESRD undergoing hemodialysis: a double-blind randomized control trial. BMC Co PubMed
- Husain I, Dale OR, Idrisi M, et al. Evaluation of the Herb-Drug Interaction (HDI) Potential of Zingiber officinale and Its Major Phytoconstituents. J Agric Food Chem. 2023;71(19):7521-7534.
- Committee on Practice Bulletins-Obstetrics. ACOG Practice Bulletin No. 189: Nausea And Vomiting Of Pregnancy. Obstet Gynecol. 2018;131(1):e15-e30. PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
Oats 13 references
- Cooper SG, Tracey EJ. Small-bowel obstruction caused by oat-bran bezoar. N Engl J Med 1989;320:1148-9. DOI
- Pick ME, Hawrysh ZJ, Gee MI, et al. Oat bran concentrate bread products improve long-term control of diabetes: a pilot study. J Am Diet Assoc 1996;96:1254-61. PubMed
- Braaten JT, Scott FW, Wood PJ, et al. High beta-glucan oat bran and oat gum reduce postprandial blood glucose and insulin in subjects with and without type 2 diabetes. Diabet Med 1994;11:312-8.
- Rosario PG, Gerst PH, Prakash K, Albu E. Dentureless distention: oat bran bezoars cause obstruction. J Am Geriatr Soc 1990;38:608. PubMed
- Food and Drug Administration. Food labeling: health claims: oats and coronary heart disease. Fed Regist 1996;61:296-313.
- Foulke J. FDA Allows Whole Oat Foods To Make Health Claim on Reducing the Risk of Heart Disease. FDA Talk Paper. 1997. Available at: http://www.fda.gov/bbs/topics/ANSWERS/ANS00782.html.
- Chandalia M, Garg A, Lutjohann D, et al. Beneficial effects of high dietary fiber intake in patients with type 2 diabetes mellitus. N Engl J Med 2000;342:1392-8. PubMed
- Lembo A, Camilleri M. Chronic constipation. N Engl J Med 2003;349:1360-8. . PubMed
- De Paz Arranz S, Perez Montero A, Remon LZ, Molero MI. Allergic contact urticaria to oatmeal. Allergy 2002;57:1215. . PubMed
- Delgado G, Kleber ME, Krämer BK, et al. Dietary intervention with oatmeal in patients with uncontrolled type 2 diabetes mellitus - A crossover study. Exp Clin Endocrinol Diabetes. 2019;127(9):623-629. PubMed
- Sobhan M, Hojati M, Vafaie SY, Ahmadimoghaddam D, Mohammadi Y, Mehrpooya M. The efficacy of colloidal oatmeal cream 1% as add-on therapy in the management of chronic irritant hand eczema: A double-blind study. Clin Cosmet Investig Dermatol. 2020;13:241-25
- Hou Q, Li Y, Li L, Cheng G, Sun X, Li S, Tian H. The metabolic effects of oats intake in patients with type 2 diabetes: A systematic review and meta-analysis. Nutrients. 2015;7(12):10369-87. PubMed
- González-Afonso M, Cañas JA, Sastre B, et al. A Case of Anaphylaxis After Ingestion of Oats: Research Into New Allergens. J Investig Allergol Clin Immunol 2022;32(6):506-508. PubMed
Pumpkin 5 references
- Marks L, Partin AW, Epstein JI, et al. Effects of a saw palmetto herbal blend in men with symptomatic benign prostatic hyperplasia. J Urol 2000;163:1451-6. DOI
- Cho YH, Lee SY, Jeong DW, et al. Effect of pumpkin seed oil on hair growth in men with androgenetic alopecia: a randomized, double-blind, placebo-controlled trial. Evid Based Complement Alternat Med 2014;2014:549721. PubMed
- Vahlensieck W, Theurer C, Pfitzer E, Patz B, Banik N, Engelmann U. Effects of pumpkin seed in men with lower urinary tract symptoms due to benign prostatic hyperplasia in the one-year, randomized, placebo-controlled GRANU study. Urol Int 2015;94(3):286-95 PubMed
- Assouly P. Hair loss associated with cucurbit poisoning. JAMA Dermatol. 2018 May 1;154(5):617-618. PubMed
- Gawryjolek J, Ludwig H, Zbikowska-Götz M, Bartuzi Z, Krogulska A. Anaphylaxis after consumption of pumpkin seeds in a 2-y-old child tolerant to its pulp: A case study. Nutrition 2021;89:111272. PubMed
Lactobacillus Delbrueckii 9 references
- Pierce A. The American Pharmaceutical Association Practical Guide to Natural Medicines. New York: The Stonesong Press, 1999:19.
- Rossi F, Amadoro C, Gasperi M, Colavita G. Lactobacilli infection case reports in the last three years and safety implications. Nutrients. 2022;14(6):1178. PubMed
- Ranchal P, Gupta R, Goldberg R, A Lobo S, Pascual A, El Khoury MY. Penicillin-sensitive Lactobacillus jensenii bacteremia. Am J Ther 2021;28(2):e250-e252. PubMed
- Grazioli-Gauthier L, Rigamonti E, Leo LA, Martinetti Lucchini G, Lo Priore E, Bernasconi E. Lactobacillus jensenii mitral valve endocarditis: Case report, literature review and new perspectives. IDCases 2022;27:e01401. PubMed
- Toprak NU, Bozan T, Yilmaz S, Buyukbayrak EE, Tigen ET. Polymicrobial bacteremia due to Lactobacillus jensenii and Veillonella montpellierensis in a pregnant patient; case report and review of literature. Anaerobe 2022;75:102576. PubMed
- Chazan B, Raz R, Shental Y, Sprecher H, Colodner R. Bacteremia and pyelonephritis caused by Lactobacillus jensenii in a patient with urolithiasis. Isr Med Assoc J 2008;10(2):164-5.
- Neonakis IK, Skamagkas I, Stafylaki D, Maraki S. Lactobacillus delbrueckii urinary tract infection in a male patient: a case report. Germs 2022;12(2):304-307. PubMed
- Maillet F, Passeron A, Podglajen I, Ranque B, Pouchot J. Lactobacillus delbrueckii urinary tract infection in a male patient. Med Mal Infect 2019;49(3):226-228. PubMed
- Darbro BW, Petroelje BK, Doern GV. Lactobacillus delbrueckii as the cause of urinary tract infection. J Clin Microbiol 2009;47(1):275-7.
See these in context on the Lactobacillus Delbrueckii monograph →
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC