
AcneXX Ingredients & Drug Interactions
What is this page for?
First and foremost: checking AcneXX against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
AcneXX is a dietary supplement by Viatrexx Bio Incorporated with 14 active ingredients. Its ingredients are commonly taken for zinc deficiency, immune support, cold symptoms.Based on those ingredients, 1,374 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Echinacea, Gotu Kola, Vitamin A. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against AcneXX by Viatrexx Bio Incorporated
Ask about any prescription or over-the-counter medication and we check it for interactions with AcneXX by Viatrexx Bio Incorporated — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of AcneXX by Viatrexx Bio Incorporated
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Low disclosure
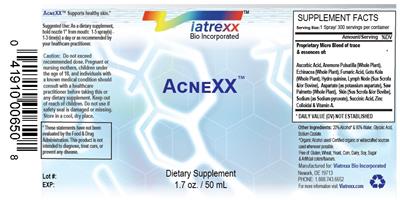
AcneXX contains 14 ingredients, 9 of which we have data on. The active players are Zinc, which supports skin and immune function; Ascorbic Acid (Vitamin C), an antioxidant; Vitamin A for skin health; Gotu Kola, a plant used in traditional medicine for wound healing; Echinacea, an herb; Saw Palmetto, used for prostate and urinary health; Aspartate, an amino acid; and Sodium.
The product also holds Fumaric Acid, Succinic Acid, Hydroquinine, Lymph Node, and Skin, for which we have no interaction or safety data on file. Inactive ingredients—alcohol, water, glycolic acid, and sodium oxalate—are listed as excipients.
Does it work?
Moderate evidence
Evidence for this product's purpose (acne) is mixed and limited. Zinc is rated Possibly Effective for acne.
Ascorbic Acid (Vitamin C) is not specifically rated for acne in our data. Vitamin A is rated Possibly Effective for aging skin but carries its own rating for acne is not on file.
Gotu Kola shows Possibly Ineffective for radiation dermatitis and no acne rating. Echinacea has no effectiveness rating for skin conditions—its highest ratings are 'Insufficient Reliable Evidence' across the conditions we track.
Saw Palmetto is not rated for acne or skin. Aspartate is not rated for acne or skin.
We hold no effectiveness data for Fumaric Acid, Succinic Acid, Hydroquinine, Lymph Node, or Skin. If acne is your goal, this product's evidence base is narrow.
How safe is it?
Well-documented data
Zinc is generally well tolerated in doses below 40 mg daily for adults, but doses above that risk copper deficiency and related anemia. Oral side effects—nausea, diarrhea, metallic taste, abdominal cramps—are dose-related.
Ascorbic Acid is generally safe at normal doses but high doses (above 2 grams daily) can cause abdominal cramps, diarrhea, heartburn, nausea, and kidney stones in those prone to them. Vitamin A is well tolerated below its upper limit (10,000 IU daily for adults) but high doses cause serious liver toxicity, headache, and birth defects—it is rated Possibly Unsafe in pregnancy and lactation.
Gotu Kola is generally well tolerated short-term but carries rare reports of liver damage and is rated Possibly Safe in pregnancy and should be avoided in lactation. Pulsatilla is toxic in its fresh form and is rated Likely Unsafe in both pregnancy and lactation.
Echinacea is well tolerated short-term but can trigger allergic reactions (especially in people sensitive to ragweed) and rare hepatitis; pregnancy rating is Possibly Safe but no lactation data exists. Saw Palmetto is well tolerated but rarely causes fixed drug eruptions and is rated Likely Unsafe in pregnancy and lactation.
Aspartate and Sodium have limited long-term safety data at supplement doses; Aspartate is rated Possibly Unsafe in pregnancy and lactation, and Sodium is generally fine at normal intake but can worsen heart and kidney disease at high levels. We hold no safety data for Fumaric Acid, Succinic Acid, Hydroquinine, Lymph Node, or Skin.
Meds to double-check
Major interaction found
Before taking AcneXX, double-check with your pharmacist if you take retinoid skin medications (isotretinoin, tretinoin, adapalene) — Major risk of vitamin A toxicity. Check if you use blood thinners (warfarin, others), blood pressure medications, HIV medications (especially integrase inhibitors, protease inhibitors), cancer chemotherapy, tetracycline or quinolone antibiotics, cephalexin, penicillamine, lithium, oral contraceptives or hormone therapy, or any immunosuppressant.
The ingredient interactions are substantial.
The bottom line
Scorecard at a glanceFormula with limited ingredient disclosure with some supporting evidence for its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
AcneXX is a multi-ingredient product with limited evidence for acne and serious interaction risks—especially with retinoids, which create a Major hazard. Anyone taking prescription medications, blood thinners, HIV drugs, cancer therapy, hormonal contraceptives, lithium, or blood pressure drugs must check their exact medications with our tool before starting.
Those pregnant or breastfeeding should talk with their pharmacist or doctor first, given Pulsatilla's unsafe rating in both and Vitamin A's teratogenic risk.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 9 of 14 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jun 20, 2024.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about AcneXX, straight from the product label.
| Brand | Viatrexx Bio Incorporated |
|---|---|
| Barcode (UPC) | 041910006508 |
| Net contents | 1.7 Ounce(s); 50 mL |
| Market status | On market |
| Date entered into DSLD | Jun 20, 2024 |
| DSLD ID | 309863 |
| Product type | Other Combinations |
| Supplement form | Liquid |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Gluten Free, Dairy Free, Sugar Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for AcneXX by Viatrexx Bio Incorporated, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Zinc | 0 NP | -- |
| Ascorbic Acid | 0 NP | -- |
| Vitamin A | 0 NP | -- |
| Fumaric Acid | 0 NP | -- |
| Succinic Acid | 0 NP | -- |
| Gotu Kola | 0 NP | -- |
| Proprietary Micro Blend of Trace and Essences | 0 NP | -- |
| Pulsatilla vulgaris | 0 NP | -- |
| Echinacea | 0 NP | -- |
| Hydroquinine | 0 NP | -- |
| Lymph Node | 0 NP | -- |
| Aspartate | 0 NP | -- |
| Saw Palmetto | 0 NP | -- |
| Skin | 0 NP | -- |
| Sodium | 0 NP | -- |
Other ingredients: Alcohol, Water, Glycolic Acid, Sodium Oxalate
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formulation
Supports health skin.
Organic alcohol used/certified organic or wildcrafted sources used whenever possible.
Free of: Gluten, wheat, yeast, corn, dairy, soy, sugar & artificial colors/flavours.
Suggested/Recommended/Usage/Directions
Suggested use: As a dietary supplement, hold nozzle 1" from mouth: 1-5 spray(s) - 1-3 time(s) a day or as recommended by your healthcare practitioner.
Precautions
Caution: Do not exceed recommended dose.
Pregnant or nursing mothers, children under the age of 18, and individuals with a known medical condition should consult with a healthcare practitioner before taking this or any dietary supplement.
Pregnant or nursing mothers, children under the age of 18, and individuals with a known medical condition should consult with a healthcare practitioner before taking this or any dietary supplement. Keep out of reach of children.
Do not use if safety seal is damaged or missing.
Storage
Store in a cool, dry place.
FDA Disclaimer Statement
These statements have not been evaluated by the Food & Drug Administration. This product is not intended to diagnose, treat, cure, or prevent any disease.
FDA Statement of Identity
Dietary Supplement
General Statements
For more information visit: Viatrexx.com
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
AcneXX by Viatrexx Bio Incorporated label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in AcneXX by Viatrexx Bio Incorporated
These are the 14 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Spray(s) Dosage formLiquid Servings per container300 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Proprietary Micro Blend of Trace and Essences
- › Zinc
- › Ascorbic Acid
- › Vitamin A
- › Fumaric Acid
- › Succinic Acid
- › Gotu Kola
- › Pulsatilla vulgaris
- › Echinacea
- › Hydroquinine
- › Lymph Node
- › Aspartate
- › Saw Palmetto
- › Skin
- › Sodium
Other (inactive) ingredients: Alcohol, Water, Glycolic Acid, Sodium Oxalate. These complete the product’s ingredient list but are not active constituents.
AcneXX by Viatrexx Bio Incorporated Drug Interactions
HelloPharmacist Interaction Report
AcneXX by Viatrexx Bio Incorporated can interact with a number of medications.
The most serious interaction involves Vitamin A and retinoids (drugs like isotretinoin, tretinoin, and adapalene) — taking them together raises vitamin A to toxic levels and creates a Major risk of serious harm.
Read the full breakdown — every affected drug type, severity by severity
Moderate interactions span multiple drug types. Zinc interferes with quinolone antibiotics, cephalexin (Keflex), tetracycline antibiotics, penicillamine, ritonavir, integrase inhibitors, and the HIV combination bictegravir/emtricitabine/tenofovir alafenamide — reducing their absorption and effectiveness.
Ascorbic Acid (Vitamin C) can raise estrogen levels, interfere with certain cancer chemotherapy drugs, increase aluminum absorption, reduce warfarin effectiveness at high doses, and affect indinavir and levothyroxine. Vitamin A at high doses also theoretically increases bleeding risk with warfarin and can raise the risk of a serious brain swelling condition (pseudotumor cerebri) if taken with tetracyclines.
Gotu Kola may add to sedation from CNS depressants and carry liver concerns if combined with hepatotoxic drugs. Echinacea affects caffeine metabolism and interacts with several cancer drugs and HIV medications.
Saw Palmetto may reduce contraceptive and hormone effectiveness and increase bleeding risk with blood thinners. Sodium can interfere with blood pressure drugs, lithium, and other medications.
We could not check Fumaric Acid, Succinic Acid, Hydroquinine, Lymph Node, or Skin for interactions — no data is on file for these ingredients. Pulsatilla has no documented interactions with medications, though it carries serious safety concerns in pregnancy and lactation.
Alone, these interactions span 1,354 individual medications. Use the medication checker on this page to run your exact prescriptions and over-the-counter drugs against this product before you start.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against AcneXX?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in AcneXX interact with 1,374 drugs. Click any drug to see the details.
7 of the 14 ingredients in AcneXX interact with drugs. Each result below shows which ingredient is responsible. Echinacea Gotu Kola Vitamin A Ascorbic Acid Sodium Saw Palmetto Zinc
AcitretinSoriatane
How Acitretin interacts with AcneXX — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Acitretin interactionAlitretinoinPanretin
How Alitretinoin interacts with AcneXX — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Alitretinoin interactionBexaroteneTargretin
How Bexarotene interacts with AcneXX — through 2 ingredients. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Bexarotene interactionEchinaceaCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Echinacea may induce hepatic CYP3A4 and inhibit intestinal CYP3A4.
Read the full Echinacea + Bexarotene interactionHalobetasol Propionate,tazaroteneDuobrii
How Halobetasol Propionate,tazarotene interacts with AcneXX — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Halobetasol Propionate,tazarotene interactionIsotretinoinAbsorica, Accutane, Amnesteem, Claravis, Roaccutane, Sotret
How Isotretinoin interacts with AcneXX — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Isotretinoin interactionTazaroteneArazlo, Avage, Fabior, Tazorotene, Zorac
How Tazarotene interacts with AcneXX — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Tazarotene interactionTretinoinAltreno, Renova, Retin-A, Vesanoid
How Tretinoin interacts with AcneXX — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Tretinoin interactionTretinoin, Benzoyl PeroxideTwyneo
How Tretinoin, Benzoyl Peroxide interacts with AcneXX — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Tretinoin, Benzoyl Peroxide interactionEtretinateTegison
How Etretinate interacts with AcneXX — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Etretinate interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with AcneXX — through 3 ingredients. Tap an ingredient for the detail:
EchinaceaImmunosuppressants Moderate
Interaction Summary
Echinacea has immunostimulant activity which may interfere with immunosuppressant therapy.
Read the full Echinacea + 6-mercaptopurine interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + 6-mercaptopurine interactionGotu KolaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking gotu kola with hepatotoxic drugs might have additive adverse effects.
Read the full Gotu Kola + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with AcneXX — through 1 ingredient. Tap an ingredient for the detail:
EchinaceaCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Echinacea may induce hepatic CYP3A4 and inhibit intestinal CYP3A4.
Read the full Echinacea + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with AcneXX — through 2 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Abacavir Sulfate, Dolutegravir, Lamivudine interactionGotu KolaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking gotu kola with hepatotoxic drugs might have additive adverse effects.
Read the full Gotu Kola + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with AcneXX — through 2 ingredients. Tap an ingredient for the detail:
Gotu KolaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking gotu kola with hepatotoxic drugs might have additive adverse effects.
Read the full Gotu Kola + Abacavir, Lamivudine interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Abacavir, Lamivudine interactionAbciximabReoPro
How Abciximab interacts with AcneXX — through 1 ingredient. Tap an ingredient for the detail:
Saw PalmettoAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Saw palmetto might increase the risk of bleeding with anticoagulant or antiplatelet drugs.
Read the full Saw Palmetto + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with AcneXX — through 1 ingredient. Tap an ingredient for the detail:
EchinaceaCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Echinacea may induce hepatic CYP3A4 and inhibit intestinal CYP3A4.
Read the full Echinacea + Abemaciclib interactionAbiraterone
How Abiraterone interacts with AcneXX — through 3 ingredients. Tap an ingredient for the detail:
EchinaceaCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Echinacea may induce hepatic CYP3A4 and inhibit intestinal CYP3A4.
Read the full Echinacea + Abiraterone interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Abiraterone interactionGotu KolaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking gotu kola with hepatotoxic drugs might have additive adverse effects.
Read the full Gotu Kola + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with AcneXX — through 3 ingredients. Tap an ingredient for the detail:
Gotu KolaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking gotu kola with hepatotoxic drugs might have additive adverse effects.
Read the full Gotu Kola + Abiraterone Acetate interactionEchinaceaCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Echinacea may induce hepatic CYP3A4 and inhibit intestinal CYP3A4.
Read the full Echinacea + Abiraterone Acetate interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with AcneXX — through 2 ingredients. Tap an ingredient for the detail:
Saw PalmettoAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Saw palmetto might increase the risk of bleeding with anticoagulant or antiplatelet drugs.
Read the full Saw Palmetto + Abrocitinib interactionEchinaceaImmunosuppressants Moderate
Interaction Summary
Echinacea has immunostimulant activity which may interfere with immunosuppressant therapy.
Read the full Echinacea + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with AcneXX — through 1 ingredient. Tap an ingredient for the detail:
EchinaceaCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Echinacea may induce hepatic CYP3A4 and inhibit intestinal CYP3A4.
Read the full Echinacea + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with AcneXX — through 2 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acarbose interactionGotu KolaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking gotu kola with hepatotoxic drugs might have additive adverse effects.
Read the full Gotu Kola + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with AcneXX — through 3 ingredients. Tap an ingredient for the detail:
Gotu KolaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking gotu kola with hepatotoxic drugs might have additive adverse effects.
Read the full Gotu Kola + Acebutolol interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acebutolol interactionSodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with AcneXX — through 1 ingredient. Tap an ingredient for the detail:
Saw PalmettoAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Saw palmetto might increase the risk of bleeding with anticoagulant or antiplatelet drugs.
Read the full Saw Palmetto + Acenocoumarol interactionAcepromazineAtravet
How Acepromazine interacts with AcneXX — through 1 ingredient. Tap an ingredient for the detail:
Gotu KolaCns Depressants Moderate
Interaction Summary
Theoretically, taking gotu kola might increase the sedative effects of CNS depressants.
Read the full Gotu Kola + Acepromazine interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with AcneXX — through 4 ingredients. Tap an ingredient for the detail:
EchinaceaCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Echinacea might inhibit the metabolism of CYP1A2 and increase plasma levels of some drugs.
Read the full Echinacea + Acetaminophen interactionGotu KolaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking gotu kola with hepatotoxic drugs might have additive adverse effects.
Read the full Gotu Kola + Acetaminophen interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen interactionAscorbic AcidAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Ascorbic Acid + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with AcneXX — through 5 ingredients. Tap an ingredient for the detail:
Gotu KolaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking gotu kola with hepatotoxic drugs might have additive adverse effects.
Read the full Gotu Kola + Acetaminophen, Aspirin interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Aspirin interactionEchinaceaCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Echinacea might inhibit the metabolism of CYP1A2 and increase plasma levels of some drugs.
Read the full Echinacea + Acetaminophen, Aspirin interactionSaw PalmettoAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Saw palmetto might increase the risk of bleeding with anticoagulant or antiplatelet drugs.
Read the full Saw Palmetto + Acetaminophen, Aspirin interactionAscorbic AcidAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Ascorbic Acid + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with AcneXX — through 5 ingredients. Tap an ingredient for the detail:
EchinaceaCytochrome P450 1a2 (cyp1a2) Substrates, Caffeine +1 Moderate
Interaction Summary
Echinacea might inhibit the metabolism of CYP1A2 and increase plasma levels of some drugs.
Read the full Echinacea + Acetaminophen, Aspirin, Caffeine interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Aspirin, Caffeine interactionGotu KolaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking gotu kola with hepatotoxic drugs might have additive adverse effects.
Read the full Gotu Kola + Acetaminophen, Aspirin, Caffeine interactionSaw PalmettoAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Saw palmetto might increase the risk of bleeding with anticoagulant or antiplatelet drugs.
Read the full Saw Palmetto + Acetaminophen, Aspirin, Caffeine interactionAscorbic AcidAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Ascorbic Acid + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with AcneXX — through 4 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionEchinaceaCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Echinacea might inhibit the metabolism of CYP1A2 and increase plasma levels of some drugs.
Read the full Echinacea + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionGotu KolaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking gotu kola with hepatotoxic drugs might have additive adverse effects.
Read the full Gotu Kola + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAscorbic AcidAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Ascorbic Acid + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, ButalbitalAxocet, Bancap, Bucet, Butex Forte, Esgic CF, Orbivan CF +5 more
How Acetaminophen, Butalbital interacts with AcneXX — through 4 ingredients. Tap an ingredient for the detail:
Gotu KolaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking gotu kola with hepatotoxic drugs might have additive adverse effects.
Read the full Gotu Kola + Acetaminophen, Butalbital interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Butalbital interactionEchinaceaCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Echinacea might inhibit the metabolism of CYP1A2 and increase plasma levels of some drugs.
Read the full Echinacea + Acetaminophen, Butalbital interactionAscorbic AcidAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Ascorbic Acid + Acetaminophen, Butalbital interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with AcneXX — through 4 ingredients. Tap an ingredient for the detail:
EchinaceaCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Echinacea might inhibit the metabolism of CYP1A2 and increase plasma levels of some drugs.
Read the full Echinacea + Acetaminophen, Butalbital, Caffeine interactionGotu KolaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking gotu kola with hepatotoxic drugs might have additive adverse effects.
Read the full Gotu Kola + Acetaminophen, Butalbital, Caffeine interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Butalbital, Caffeine interactionAscorbic AcidAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Ascorbic Acid + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with AcneXX — through 4 ingredients. Tap an ingredient for the detail:
EchinaceaCaffeine, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Echinacea can increase plasma levels of caffeine by inhibiting its metabolism.
Read the full Echinacea + Acetaminophen, Butalbital, Caffeine, Codeine interactionGotu KolaCns Depressants, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking gotu kola might increase the sedative effects of CNS depressants.
Read the full Gotu Kola + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acetaminophen, Butalbital, Caffeine, Codeine interactionAscorbic AcidAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Ascorbic Acid + Acetaminophen, Butalbital, Caffeine, Codeine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in AcneXX with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Echinacea
Caffeine
Echinacea can increase plasma levels of caffeine by inhibiting its metabolism.
Echinacea seems to increase plasma concentrations of caffeine by around 30%. This is likely due to inhibition of cytochrome P450 1A2 (CYP1A2) by echinacea.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Echinacea might inhibit the metabolism of CYP1A2 and increase plasma levels of some drugs.
Echinacea appears to inhibit CYP1A2 enzymes in humans. Additionally, echinacea seems to increase plasma concentrations of caffeine, a CYP1A2 substrate, by around 30%. Theoretically, echinacea might increase levels of other drugs metabolized by CYP1A2.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Echinacea may induce hepatic CYP3A4 and inhibit intestinal CYP3A4. This may increase or decrease levels of drugs metabolized by CYP3A4.
Several clinical trials have shown that taking echinacea for up to one month does not significantly affect the metabolism of various CYP3A4 substrates, including midazolam, docetaxel, etravirine, lopinavir-ritonavir, and darunavir-ritonavir. However, other clinical research shows that echinacea may increase the clearance of midazolam, suggesting that echinacea might induce CYP3A4. The discrepancy is thought to be due to differing effects of echinacea on intestinal versus hepatic CYP3A4 enzymes. Echinacea appears to induce hepatic CYP3A4 but inhibit intestinal CYP3A4. In some cases, these effects might cancel each other out, but in others, drug levels may be increased or decreased depending on the level of effect at hepatic and intestinal sites. The effect of echinacea on CYP3A4 activity may differ depending on the CYP3A4 substrate.
Etoposide (Vepesid)
Echinacea may increase levels of etoposide.
In one report, concomitant use of etoposide and echinacea was associated with more severe thrombocytopenia than the use of etoposide alone, suggesting inhibition of etoposide metabolism. Etoposide is a cytochrome P450 3A4 (CYP3A4) substrate. Echinacea has variable effects on CYP3A4, but some studies have reported inhibition of the enzyme.
Immunosuppressants
Echinacea has immunostimulant activity which may interfere with immunosuppressant therapy.
Theoretically, echinacea may interfere with immunosuppressant therapy because of its immunostimulant activity.
Darunavir (Prezista)
Theoretically, echinacea may interfere with the metabolism of darunavir; however, a small clinical study found no effect.
Darunavir is metabolized by cytochrome P450 3A4 (CYP3A4) and is administered with the CYP3A4 inhibitor ritonavir to increase its plasma concentrations. Echinacea has variable effects on CYP3A4, but administration of an E. purpurea root extract (Arkocapsulas Echinacea, Arkopharma) 500 mg four times daily for 14 days did not affect darunavir/ritonavir pharmacokinetics in 15 HIV-infected patients.
Dayquil Severe
Echinacea is reported to have varying effects on a number of Cytochrome P450 metabolizing enzymes in the liver, including CYP1A2 and CYP3A4, which play a role in acetaminophen and dextromethorphan metabolism (both contained in DayQuil Severe), respectively. Studies have reported both enzyme inhibition and induction, making it difficult to predict clinically significant drug interactions with reliability. Specific drug interaction studies reporting definitive results are rare, and potential drug interactions involving echinacea should likely be taken on a case-by-case basis. Based on what we know about how acetaminophen and dextromethorphan are metabolized, the risk of a clinically significant interaction between echinacea and DayQuil Severe is low.
Docetaxel (Taxotere)
Theoretically, echinacea may interfere with the metabolism of docetaxel; however, a small clinical study found no effect.
Docetaxel is metabolized by cytochrome P450 3A4 (CYP3A4). Echinacea has variable effects on CYP3A4, but taking E. purpurea whole plant extract (Echinaforce, A. Vogel Biopharma AG) 20 drops three times daily for 2 weeks did not alter the pharmacokinetics of docetaxel in one clinical study.
Etravirine (Intelence)
Theoretically, echinacea may interfere with the metabolism of etravirine; however, a small clinical study found no effect.
Etravirine is metabolized by cytochrome P450 3A4 (CYP3A4). Echinacea has variable effects on CYP3A4, but taking E. purpurea root extract (Arkocapsulas Echinacea, Arkopharma) 500 mg three times daily for 14 days did not alter the pharmacokinetics of etravirine in HIV-infected patients.
Lopinavir/Ritonavir (Kaletra)
Theoretically, echinacea may interfere with the metabolism of lopinavir; however, a small clinical study found no effect.
Lopinavir is metabolized by cytochrome P450 3A4 (CYP3A4) and is administered with the CYP3A4 inhibitor ritonavir to increase its plasma concentrations. Echinacea has variable effects on CYP3A4, but taking E. purpurea (Echinamide, Natural Factors Nutritional Products, Inc.) 500 mg three times daily for 14 days did not alter the pharmacokinetics of lopinavir/ritonavir in healthy volunteers.
Midazolam (Versed)
Theoretically, echinacea may increase the metabolism of intravenous midazolam.
Echinacea induces hepatic CYP3A4 and might decrease plasma levels of midazolam by about 20%, reducing the effectiveness of intravenous midazolam. Echinacea also appears to inhibit intestinal CYP3A4, which could theoretically increase the bioavailability of oral midazolam. This may cancel out the decrease in availability caused by induction of hepatic CYP3A4, such that overall plasma levels after oral administration of midazolam are not affected by echinacea.
Warfarin (Coumadin)
Echinacea seems to increase the clearance of warfarin, although the effect may not be clinically significant.
Preliminary clinical research in healthy male volunteers suggests that taking echinacea increases the clearance of the active S-isomer of warfarin after a single dose of warfarin, but there was not a clinically significant effect on the INR.
Gotu Kola
Cns Depressants
Theoretically, taking gotu kola might increase the sedative effects of CNS depressants.
In vitro research suggests that gotu kola may have sedative effects via binding of GABA receptors.
Hepatotoxic Drugs
Theoretically, taking gotu kola with hepatotoxic drugs might have additive adverse effects.
There are at least four case reports of hepatotoxicity associated with the use of gotu kola. However, more information is needed to determine if gotu kola was the causative factor in these cases.
Vitamin A
Retinoids
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Retinoids, which are vitamin A derivatives, could have additive toxic effects when taken with vitamin A supplements.
Hepatotoxic Drugs
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
The tolerable upper intake level (UL) is the highest level of intake that is likely to pose no risk of adverse effects. Doses of vitamin A above the UL can cause hepatotoxicity, ranging from elevated liver enzymes to liver failure.
Tetracycline Antibiotics
Theoretically, taking tetracycline antibiotics with high doses of vitamin A can increase the risk of pseudotumor cerebri.
Benign intracranial hypertension (pseudotumor cerebri) can occur with tetracyclines and with acute or chronic vitamin A toxicity. Case reports suggest that taking tetracyclines and vitamin A concurrently can increase the risk of this condition. Avoid high doses of vitamin A in people taking tetracyclines chronically.
Warfarin (Coumadin)
Theoretically, high doses of vitamin A could increase the risk of bleeding with warfarin.
Vitamin A toxicity is associated with hemorrhage and hypoprothrombinemia, possibly due to vitamin K antagonism. Advise patients taking warfarin to avoid doses of vitamin A above the tolerable upper intake level of 10,000 IU/day for adults.
Ascorbic Acid
Alkylating Agents
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin C have on chemotherapy.
Aluminum
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Research in animals and humans shows that vitamin C increases aluminum absorption, theoretically by chelating aluminum and keeping it in solution where it is available for absorption. In people with normal renal function, urinary excretion of aluminum will likely increase, making aluminum retention and toxicity unlikely. Patients with renal failure who take aluminum-containing compounds such as phosphate binders should avoid vitamin C supplements in doses above the recommended dietary allowances.
Antitumor Antibiotics
Theoretically, the antioxidant effects of vitamin C might reduce the effectiveness of antitumor antibiotics.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as doxorubicin. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effects, if any, antioxidants such as vitamin C have on chemotherapy.
Estrogens
Vitamin C might increase blood levels of estrogens.
Increases in plasma estrogen levels of up to 55% occur under some circumstances when vitamin C is taken concurrently with oral contraceptives or hormone replacement therapy, including topical products. It is suggested that vitamin C prevents oxidation of estrogen in the tissues, regenerates oxidized estrogen, and reduces sulfate conjugation of estrogen in the gut wall. When tissue levels of vitamin C are high, these processes are already maximized and supplemental vitamin C does not have any effect on estrogen levels. Increases in plasma estrogen levels may occur when patients who are deficient in vitamin C take supplements. Monitor these patients for estrogen-related side effects.
Fluphenazine (Prolixin)
Theoretically, vitamin C might decrease levels of fluphenazine.
In one patient there was a clinically significant decrease in fluphenazine levels when vitamin C (500 mg twice daily) was started. The mechanism is not known, and there is no further data to confirm this interaction.
Indinavir (Crixivan)
Vitamin C can modestly reduce indinavir levels.
One pharmacokinetic study shows that taking vitamin C 1 gram orally once daily along with indinavir 800 mg orally three times daily reduces the area under the concentration-time curve of indinavir by 14%. The mechanism of this interaction is unknown, but it is unlikely to be clinically significant in most patients. The effect of higher doses of vitamin C on indinavir levels is unknown.
Levothyroxine (Synthroid, Others)
Vitamin C can increase levothyroxine absorption.
Two clinical studies in adults with poorly controlled hypothyroidism show that swallowing levothyroxine with a glass of water containing vitamin C 500-1000 mg in solution reduces thyroid stimulating hormone (TSH) levels and increases thyroxine (T4) levels when compared with taking levothyroxine alone. This suggests that vitamin C increases the oral absorption of levothyroxine, possibly due to a reduction in pH.
Warfarin (Coumadin)
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Vitamin C in high doses may cause diarrhea and possibly reduce warfarin absorption. There are reports of two people who took up to 16 grams daily of vitamin C and had a reduction in prothrombin time. Lower doses of 5-10 grams daily can also reduce warfarin absorption. In many cases, this does not seem to be clinically significant. However, a case of warfarin resistance has been reported for a patient who took vitamin C 500 mg twice daily. Cessation of vitamin C supplementation resulted in a rapid increase in international normalized ratio (INR). Tell patients taking warfarin to avoid taking vitamin C in excessively high doses (greater than 10 grams daily). Lower doses may be safe, but the anticoagulation activity of warfarin should be monitored. Patients who are stabilized on warfarin while taking vitamin C should avoid adjusting vitamin C dosage to prevent the possibility of warfarin resistance.
Acetaminophen (Tylenol, Others)
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
A small pharmacokinetic study in healthy volunteers shows that taking high-dose vitamin C (3 grams) 1.5 hours after taking acetaminophen 1 gram slightly increases the apparent half-life of acetaminophen from around 2.3 hours to 3.1 hours. Ascorbic acid competitively inhibits sulfate conjugation of acetaminophen. However, to compensate, elimination of acetaminophen glucuronide and unconjugated acetaminophen increases. This effect is not likely to be clinically significant.
Aspirin
Acidification of the urine by vitamin C might increase aspirin levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction is not clinically significant.
Choline Magnesium Trisalicylate (Trilisate)
Acidification of the urine by vitamin C might increase choline magnesium trisalicylate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Niacin
Vitamin C might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as vitamin C, or to the combination. It also is not known whether it will occur in other patient populations.
Salsalate (Disalcid)
Acidification of the urine by vitamin C might increase salsalate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams/day vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Sodium
Antihypertensive Drugs
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
High intake of dietary sodium can increase systolic and diastolic blood pressure. Also, high intake of sodium may necessitate increased use of antihypertensive medications to achieve blood pressure control in some patients, such as those with chronic kidney disease.
Corticosteroids
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Mineralocorticoids and some glucocorticoids (corticosteroids) cause sodium retention. This effect is dose-related and depends on mineralocorticoid potency. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Didanosine (Videx)
Concomitant use of didanosine with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia.
Didanosine formulations contain a significant amount of sodium.
Lithium
Altering dietary intake of sodium might alter the levels and clinical effects of lithium.
High sodium intake can reduce plasma concentrations of lithium by increasing lithium excretion. Reducing sodium intake can significantly increase plasma concentrations of lithium and cause lithium toxicity in patients being treated with lithium carbonate. Stabilizing sodium intake is shown to reduce the percentage of patients with lithium level fluctuations above 0.8 mEq/L. Patients taking lithium should avoid significant alterations in their dietary intake of sodium.
Sodium Phosphates
Theoretically, concomitant use of sodium phosphate with sodium supplements might increase the risk of hypernatremia.
Use of high doses (> 45 mL in 24 hours) of sodium phosphate, such as those used for bowel cleansing before surgery, can lead to serious electrolyte disturbances, including hypernatremia. The risk of hypernatremia is highest in the elderly and people with other risk factors for electrolyte disturbances.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related complications.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium supplements or high-sodium diets, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Tolvaptan (Samsca)
Theoretically, concomitant use of tolvaptan with sodium might increase the risk of hypernatremia.
Tolvaptan is a vasopressin receptor 2 antagonist that is used to increase sodium levels in patients with hyponatremia. Patients taking tolvaptan should use caution with the use of sodium salts such as sodium chloride.
Saw Palmetto
Anticoagulant/Antiplatelet Drugs
Saw palmetto might increase the risk of bleeding with anticoagulant or antiplatelet drugs.
Saw palmetto is reported to prolong bleeding time. Theoretically, it might increase the risk of bleeding when used concomitantly with anticoagulant or antiplatelet drugs.
Contraceptive Drugs
Saw palmetto might reduce the effectiveness of contraceptive drugs.
Saw palmetto might have antiestrogenic effects. Theoretically, it might interfere with contraceptive drugs taken concomitantly.
Estrogens
Saw palmetto might reduce the effectiveness of estrogens.
Saw palmetto might have antiestrogenic effects. Theoretically, it might interfere with estrogens taken concomitantly.
Zinc
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Theoretically, zinc might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after zinc containing products.
Cephalexin (Keflex)
Zinc might decrease cephalexin levels by chelating with cephalexin in the gut and preventing its absorption.
A pharmacokinetic study shows that zinc sulfate 250 mg taken concomitantly with cephalexin 500 mg decreases peak levels of cephalexin by 31% and reduces the exposure to cephalexin by 27%. Also, taking zinc sulfate 3 hours before cephalexin decreases peak levels of cephalexin by 11% and reduces the exposure to cephalexin by 18%. By decreasing cephalexin levels, zinc might increase the risk of treatment failure. This effect does not occur when zinc is taken 3 hours after the cephalexin dose. To avoid an interaction, advise patients take zinc sulfate 3 hours after taking cephalexin.
Cisplatin (Platinol-Aq)
Theoretically, zinc might interfere with the therapeutic effects of cisplatin.
Animal research suggests that zinc stimulates tumor cell production of the protein metallothionein, which binds and inactivates cisplatin. It is not known whether zinc supplements or high dietary zinc intake can cause clinically significant interference with cisplatin therapy. Cisplatin might also increase zinc excretion.
Integrase Inhibitors
Theoretically, taking zinc along with integrase inhibitors might decrease the levels and clinical effects of these drugs.
Zinc is a divalent cation. Pharmacokinetic studies have shown that other divalent cations such as calcium and iron can decrease blood levels of the integrase inhibitor dolutegravir through chelation.
Penicillamine (Cuprimine, Depen)
Zinc might reduce the levels and clinical effects of penicillamine.
By forming an insoluble complex with penicillamine, zinc interferes with penicillamine absorption and activity. Zinc supplements reduce the efficacy of low-dose penicillamine (0.5-1 gram/day), but do not seem to affect higher doses (1-2.75 gram/day), provided dosing times are separated. Advise patients to take zinc and penicillamine at least 2 hours apart.
Quinolone Antibiotics
Zinc can decrease the levels and clinical effects of quinolones antibiotics.
Quinolones form complexes with zinc in the gastrointestinal tract, reducing absorption of both the quinolone and zinc if taken at the same time. Advise patients to take these drugs at least 2 hours before, or 4-6 hours after, zinc supplements.
Ritonavir (Norvir)
Zinc modestly reduces levels of ritonavir.
Clinical research shows that zinc might reduce serum ritonavir levels by chelating with ritonavir in the gut and preventing its absorption. In patients with HIV, ritonavir is taken with atazanavir to prevent the metabolism and increase the effects of atazanavir. A pharmacokinetic study shows that, in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate (Solvazinc tablets) 125 mg as a single dose or as multiple daily doses for 2 weeks reduces plasma levels of ritonavir by about 16%. However, atazanavir levels still remains high enough to prevent HIV virus replication. Therefore, the decrease in ritonavir levels is not likely to be clinically significant.
Tetracycline Antibiotics
Zinc might reduce levels of tetracycline antibiotics.
Tetracyclines form complexes with zinc in the gastrointestinal tract, which can reduce absorption of both the tetracycline and zinc when taken at the same time. Taking zinc sulfate 200 mg with tetracycline reduces absorption of the antibiotic by 30% to 40%. Demeclocycline and minocycline cause a similar interaction. However, doxycycline does not seem to interact significantly with zinc. Advise patients to take tetracyclines at least 2 hours before, or 4-6 hours after, zinc supplements to avoid any interactions.
Amiloride (Midamor)
Amiloride can modestly reduce zinc excretion and increase zinc levels.
Clinical research shows that amiloride can reduce urinary zinc excretion, especially at doses of 10 mg per day or more. This zinc-sparing effect can help to counteract zinc losses caused by thiazide diuretics, but it is unlikely to cause zinc toxicity at usual amiloride doses. The other potassium-sparing diuretics, spironolactone (Aldactone) and triamterene (Dyrenium), do not seem to have a zinc-sparing effect.
Atazanavir (Reyataz)
Zinc modestly reduces levels of atazanavir, although this effect does not seem to be clinically significant.
Clinical research shows that zinc might decrease serum atazanavir levels by chelating with atazanavir in the gut and preventing its absorption. Although a single dose of zinc sulfate (Solvazinc tablets) 125 mg orally does not affect atazanavir concentrations in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate 125 mg daily for 2 weeks reduces plasma levels of atazanavir by about 22% in these patients. However, despite this decrease, atazanavir levels still remain at high enough concentrations for the prevention of HIV virus replication.
Brand information
Manufacturer and brand details for AcneXX, from the product label.
Viatrexx Bio Incorporated
See all Viatrexx Bio Incorporated products- Name
- Viatrexx Bio Incorporated
- City
- Newark
- State
- DE
- ZipCode
- 19713
- Phone Number
- 1.888.743.6652
- Web Address
- Viatrexx.com
AcneXX by Viatrexx Bio Incorporated: Common Questions
Does AcneXX by Viatrexx Bio Incorporated interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Is this safe to use while pregnant or breastfeeding?
What is Gotu Kola supposed to do in this product?
Can I take this if I'm on a blood thinner like warfarin?
Does Echinacea in this product affect caffeine or energy drinks?
What side effects are most common with this product?
Is there evidence this actually works for acne?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if AcneXX is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind AcneXX’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Zinc
Interacts with 67 drugsZinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but supplements can help correct or prevent a defici...
Read the full Zinc monograph → Herb & supplement monographVitamin C
Interacts with 207 drugsVitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for immune function, collagen, and acts as an...
Read the full Vitamin C monograph → Herb & supplement monographVitamin A
Interacts with 387 drugsVitamin A is an essential nutrient important for vision, skin, immune function, and growth. Most people get enough from a balanced diet, and supplements are mainly useful for correcting a tr...
Read the full Vitamin A monograph → Herb & supplement monographGotu Kola
Interacts with 579 drugsGotu kola is a traditional Ayurvedic and Asian herb that people use for wound healing, circulation, skin problems, and as a calming or memory-supporting herb. Some early studies suggest poss...
Read the full Gotu Kola monograph → Herb & supplement monographPulsatilla
Pulsatilla is a flowering plant in the buttercup family that is most often used today in homeopathic (highly diluted) preparations. The fresh plant is toxic and irritating, so it must never...
Read the full Pulsatilla monograph → Herb & supplement monographEchinacea
Interacts with 816 drugsEchinacea is a popular herb taken to help prevent or shorten the common cold, but study results are mixed and the overall benefit appears small at best. It is generally well tolerated for sh...
Read the full Echinacea monograph → Herb & supplement monographAspartic Acid
Aspartic acid is a common amino acid your body makes on its own and gets from protein-rich foods, so a true deficiency is rare. D-aspartic acid is heavily marketed for boosting testosterone...
Read the full Aspartic Acid monograph → Herb & supplement monographSaw Palmetto
Interacts with 174 drugsSaw palmetto is a plant extract most often used for urinary symptoms linked to an enlarged prostate (BPH). The best research suggests it works no better than a placebo for most men, though i...
Read the full Saw Palmetto monograph → Herb & supplement monographSodium
Interacts with 205 drugsSodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets get more than enough—often too much—from...
Read the full Sodium monograph →Sources & How We Checked
AcneXX's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 303 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Zinc 88 references
- Barceloux DG. Zinc. J Toxicol Clin Toxicol 1999;37:279-92.
- Eby GA, Davis DR, Halcomb WW. Reduction in duration of common colds by zinc gluconate lozenges in a double-blind study. Antimicrob Agents Chemother 1984;25:20-4. DOI
- Smith DS, Helzner EC, Nuttall CE Jr, et al. Failure of zinc gluconate in treatment of acute upper respiratory tract infections. Antimicrob Agents Chemother 1989;33:646-8. PubMed
- Blondeau JM. Expanded activity and utility of the new fluoroquinolones: a review. Clin Ther 1999;21:3-40. PubMed
- Reyes AJ, Olhaberry JV, Leary WP, et al. Urinary zinc excretion, diuretics, zinc deficiency and some side-effects of diuretics. S Afr Med J 1983;64:936-41.
- Kugelmas M. Preliminary observation: oral zinc sulfate replacement is effective in treating muscle cramps in cirrhotic patients. J Am Coll Nutr 2000;19:13-5. PubMed
- Hebel SK, ed. Drug Facts and Comparisons. 52nd ed. St. Louis: Facts and Comparisons, 1998.
- Chan S, Gerson B, Subramaniam S. The role of copper, molybdenum, selenium, and zinc in nutrition and health. Clin Lab Med 1998;18:673-85. DOI
- Brewer GJ, Yuzbasiyan-Gurkan V, Johnson V, et al. Treatment of Wilson's disease with zinc: XI. Interaction with other anticopper agents. J Am Coll Nutr 1993;12:26-30. PubMed
- Fosmire GJ. Zinc toxicity. Am J Clin Nutr 1990;51:225-7.
- Lomaestro BM, Bailie GR. Absorption interactions with fluoroquinolones. 1995 update. Drug Saf 1995;12:314-33. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Seelig MS. Auto-immune complications of D-penicillamine - A possible result of zinc and magnesium depletion and of pyridoxine inactivation. J Am Coll Nutr 1982;1:207-14. PubMed
- Neuvonen PJ. Interactions with the absorption of tetracyclines. Drugs 1976;11:45-54.. PubMed
- Hirt M, Nobel S, Barron E. Zinc nasal gel for the treatment of common cold symptoms: A double-blind, placebo-controlled trial. Ear Nose Throat J 2000;79:778-82.. DOI
- Simkin PA. Oral zinc sulphate in rheumatoid arthritis. Lancet 1976;2:539-42. PubMed
- Wray D. A double-blind trial of systemic zinc sulfate in recurrent aphthous stomatitis. Oral Surg Oral Med Oral Pathol 1982;53:469-72. PubMed
- Douglas RM, Miles HB, Moore BW, et al. Failure of effervescent zinc acetate lozenges to alter the course of upper respiratory tract infections in Australian adults. Antimicrob Agents Chemother 1987;31:1263-5. PubMed
- Lagiou P, Wuu J, Trichopoulou A, et al. Diet and benign prostatic hyperplasia: a study in Greece. Urology 1999;54:284-90. PubMed
- Ewing CI, Gibbs AC, Ashcroft C, David TJ. Failure of oral zinc supplementation in atopic eczema. Eur J Clin Nutr 1991;45:507-10.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Age-Related Eye Disease Study Research Group. A randomized, placebo-controlled, clinical trial of high-dose supplementation with vitamins C and E, beta carotene, and zinc for age-related macular degeneration and vision loss. AREDS report no. 8. Arch Oph
- Greenberg JE, Lynn M, Kirsner RS, et al. Mucocutaneous pigmented macule as a result of zinc deposition. J Cutan Pathol 2002;29:613-5. PubMed
- Godfrey HR, Godfrey NJ, Godfrey JC, Riley D. A randomized clinical trial on the treatment of oral herpes with topical zinc oxide/glycine. Altern Ther Health Med 2001;7:49-56.
- Turner RB. Ineffectiveness of intranasal zinc gluconate for prevention of experimental rhinovirus colds. Clin Infect Dis 2001;33:1865-70. PubMed
- Belongia EA, Berg R, Liu K. A randomized trial of zinc nasal spray for the treatment of upper respiratory illness in adults. Am J Med 2001;111:103-8. PubMed
- Mossad SB. Effect of zincum gluconicum nasal gel on the duration and symptom severity of the common cold in otherwise healthy adults. QJM 2003;96:35-43. DOI
- Leitzmann MF, Stampfer MJ, Wu K, et al. Zinc supplement use and risk of prostate cancer. J Natl Cancer Inst 2003;95:1004-7.. PubMed
- Jafek BW, Linschoten M, Murrow BW. Zicam Induced Anosmia. American Rhinologic Society 49th Annual Fall Scientific Meeting abstract. Orlando, Florida. September 20, 2003. http://app.american-rhinologic.org/programs/2003ARSFallProgram071503.pdf (Accessed 24
- Uebayashi H, Hatanaka T, Kanemura F, Tonosaki K. Acute anosmia in the mouse: behavioral discrimination among the four basic taste substances. Physiol Behav 2001;72:291-6.. PubMed
- Barrett S. Zicam Marketers Sued. United States District Court Western District of Michigan Southern Division, Filed October 14, 2003, Case No. 4:03CV0146.
- Bilici M, Yildirim F, Kandil S, et al. Double-blind, placebo-controlled study of zinc sulfate in the treatment of attention deficit hyperactivity disorder. Prog Neuropsychopharmacol Biol Psychiatry 2004;28:181-90.. PubMed
- Polk RE, Healy DP, Sahai J, et al. Effect of ferrous sulfate and multivitamins with zinc on absorption of ciprofloxacin in normal volunteers. Antimicrob Agents Chemother 1989;33:1841-4. PubMed
- Mery C, Delrieu F, Ghozlan R, et al. Controlled trial of D-penicillamine in rheumatoid arthritis. Dose effect and the role of zinc. Scand J Rheumatol 1976;5:241-7. PubMed
- Penttila O, Hurme H, Neuvonen PJ. Effect of zinc sulfate on the absorption of tetracycline and doxycycline in man. Eur J Clin Pharmacol 1975;9:131-4.
- Kondo Y, Yamagata K, Satoh M, et al. Optimal administration schedule of cisplatin for bladder tumor with minimal induction of metallothionein. J Urol 2003;170:2467-70. PubMed
- Doz F, Berens ME, Deschepper CF, et al. Experimental basis for increasing the therapeutic index of cis-diamminedicarboxylatocyclobutaneplatinum(II) in brain tumor therapy by a high-zinc diet. Cancer Chemother Pharmacol 1992;29:219-26.
- Wester PO. Urinary zinc excretion during treatment with different diuretics. Acta Med Scand 1980;208:209-12. PubMed
- Golik A, Modai D, Weissgarten J, et al. Hydrochlorothiazide-amiloride causes excessive urinary zinc excretion. Clin Pharmacol Ther 1987;42:42-4. PubMed
- Leary WP, Reyes AJ, Van der Byl K. Urinary magnesium and zinc excretion after two different single doses of amiloride in healthy adults. Curr Ther Res 1983;34:205-16.
- McBride K, Slotnick B, Margolis FL. Does intranasal application of zinc sulfate produce anosmia in the mouse? An olfactometric and anatomical study. Chem Senses 2003;28:659-70. PubMed
- Burd GD. Morphological study of the effects of intranasal zinc sulfate irrigation on the mouse olfactory epithelium and olfactory bulb. Microsc Res Tech 1993;24:195-213. PubMed
- Ducray A, Bondier JR, Michel G, et al. Recovery following peripheral destruction of olfactory neurons in young and adult mice. Eur J Neurosci 2002;15:1907-17. PubMed
- Mayer AD, Rosenblatt JS. Peripheral olfactory deafferentation of the primary olfactory system in rats using ZnSO4 nasal spray with special reference to maternal behavior. Physiol Behav 1993;53:587-92. PubMed
- DeCook CA, Hirsch AR. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Tisdall FF, Brown A, Defries RD. Persistent anosmia following zinc sulfate nasal spraying. JPed 1938;18:60-2. DOI
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Public Health Advisory. Loss of sense of smell with intranasal cold remedies containing zinc. U.S. Food and Drug Administration, June 16, 2009. Available at: http://www.fda.gov/Drugs/DrugSafety/PublicHealthAdvisories/ucm166059.htm (Accessed 16 June 2009)
- Dooren JC. FDA warns against use of Zicam. The Wall Street Journal, June 16, 2009. Available at: http://online.wsj.com/article/SB124516778692319231.html#mod=djemHL?mg=com-wsj (Accessed 16 June 2009).
- Alexander TH, Davidson TM. Intranasal zinc and anosmia: the zinc-induced anosmia syndrome. Laryngoscope 2006;116:217-20.
- Health Canada / GlaxoSmithKline Consumer Healthcare. Association of long-term, excessive use of zinc-containing Poli-Grip products with myeloneuropathy and blood dyscrasias. February 18, 2010. Available at: http://hc-sc.gc.ca/dhp-mps/alt_formats/pdf/medef
- GlaxoSmithKline Consumer Advisory. GlaxoSmithKline (GSK) warns about a potential health risk associated with long-term, excessive use of GSK's zinc-containing denture adhesives Super Polygrip Original, Ultra Fresh and Extra Care. February 18, 2010. Availa
- Science M, Johnstone J, Roth DE, et al. Zinc for the treatment of the common cold: a systematic review and meta-analysis of randomized controlled trials. CMAJ 2012;184:E551-61. PubMed
- Castilla-Higuero, L., Romero-Gomez, M., Suarez, E., and Castro, M. Acute hepatitis after starting zinc therapy in a patient with presymptomatic Wilson's disease. Hepatology 2000;32(4 Pt 1):877. PubMed
- Sharquie, K. E., Najim, R. A., Farjou, I. B., and Al Timimi, D. J. Oral zinc sulphate in the treatment of acute cutaneous leishmaniasis. Clin.Exp.Dermatol. 2001;26(1):21-26. PubMed
- Dreno, B., Moyse, D., Alirezai, M., Amblard, P., Auffret, N., Beylot, C., Bodokh, I., Chivot, M., Daniel, F., Humbert, P., Meynadier, J., and Poli, F. Multicenter randomized comparative double-blind controlled clinical trial of the safety and efficacy of
- Moore, R. Bleeding gastric erosion after oral zinc sulphate. Br.Med J 3-25-1978;1(6115):754. PubMed
- Jafek, B. W., Linschoten, M. R., and Murrow, B. W. Anosmia after intranasal zinc gluconate use. Am J Rhinol. 2004;18(3):137-141. DOI
- Simonart, T. and de, Maertelaer, V. Systemic treatments for cutaneous warts: a systematic review. J Dermatolog.Treat. 2012;23(1):72-77. PubMed
- Cochran, R. J., Tucker, S. B., and Flannigan, S. A. Topical zinc therapy for acne vulgaris. Int.J Dermatol. 1985;24(3):188-190. DOI
- Morgan, A. A. Bleeding gastric erosion after oral zinc sulphate. Br.Med.J. 5-13-1978;1(6122):1283-1284. PubMed
- Murphy, J. V. Intoxication following ingestion of elemental zinc. JAMA 6-22-1970;212(12):2119-2120.
- Lang, C. J., Rabas-Kolominsky, P., Engelhardt, A., Kobras, G., and Konig, H. J. Fatal deterioration of Wilson's disease after institution of oral zinc therapy. Arch Neurol. 1993;50(10):1007-1008. PubMed
- Fjellner, B. Drug-induced lupus erythematosus aggravated by oral zinc therapy. Acta Derm.Venereol. 1979;59(4):368-370. DOI
- Varas Lorenzo, M. J. Zinc acexamate and ranitidine in the short- and mid-term management of gastroduodenal ulcers. Curr Ther Res 21986;39:19-29.
- Bosch, F. and Jimenez, E. Post-marketing surveillance of zinc acexamate in peptic ulcer treatment. Clin Trials J 1990;27:301-312.
- DeCook, C. A. and Hirsch, A. R. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Crown LA, May JA. Zinc toxicity: denture adhesives, bone marrow failure and polyneuropathy. Tenn Med. 2012 Feb;105(2):39-40, 42.
- Dadamio J, Van Tournout M, Teughels W, Dekeyser C, Coucke W, Quirynen M. Efficacy of different mouthrinse formulations in reducing oral malodour: a randomized clinical trial. J Clin Periodontol. 2013 May;40(5):505-13. PubMed
- Moyle G, Else L, Jackson A, Back D, Yapa MH, Seymour N, Ringner-Nackter L, Karolia Z, Gazzard B, Boffito M. Coadministration of atazanavir-ritonavir and zinc sulfate: impact on hyperbilirubinemia and pharmacokinetics. Antimicrob Agents Chemother. 2013 Aug PubMed
- Zittel S, Ufer F, Gerloff C, Münchau A, Rosenkranz M. Severe myelopathy after denture cream use--is copper deficiency or excess zinc the cause? Clin Neurol Neurosurg. 2014 Jun;121:17-8. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Guidelines for the Use of Antiretroviral Agents in HIV-1-Infected Adults and Adolescents: Drug Interactions between Integrase Inhibitors and Other Drugs. AIDSinfo. July 14, 2016. Available at: https://aidsinfo.nih.gov/guidelines/html/1/adult-and-adolescen
- Ding Y, Jia YY, Li F, et al. The effect of staggered administration of zinc sulfate on the pharmacokinetics of oral cephalexin. Br J Clin Pharmacol. 2012 Mar;73(3):422-7. PubMed
- Fallah R, Sabbaghzadegan S, Karbasi SA, Binesh F. Efficacy of zinc sulfate supplement on febrile seizure recurrence prevention in children with normal serum zinc level: A randomised clinical trial. Nutrition. 2015;31(11-12):1358-61. PubMed
- Lazzerini M, Wanzira H. Oral zinc for treating diarrhoea in children. Cochrane Database Syst Rev. 2016;12:CD005436. PubMed
- Mahmoud AM, Al-Alem U, Dabbous F, et al. Zinc intake and risk of prostate cancer: Case-control study and meta-analysis. PLoS One. 2016;11(11):e0165956. PubMed
- Nagraj SK, George RP, Shetty N, Levenson D, Ferraiolo DM, Shrestha A. Interventions for managing taste disturbances. Cochrane Database Syst Rev. 2017 Dec 20;12(12):CD010470. PubMed
- Yee BE, Richards P, Sui JY, Marsch AF. Serum zinc levels and efficacy of zinc treatment in acne vulgaris: A systematic review and meta-analysis. Dermatol Ther. 2020:e14252. PubMed
- Janyajirawong R, Vilaichone RK, Sethasine S. Efficacy of zinc supplement in minimal hepatic encephalopathy: A prospective, randomized controlled study (Zinc-MHE Trial). Asian Pac J Cancer Prev 2021;22(9):2879-2887. PubMed
- Nakano M, Nakamura Y, Miyazaki A, Takahashi J. Zinc pharmacotherapy for elderly osteoporotic patients with zinc deficiency in a clinical setting. Nutrients 2021;13(6):1814. PubMed
- Tolino E, Skroza N, Mambrin A, et al. An open-label study comparing oral zinc to lymecycline in the treatment of acne vulgaris. J Clin Aesthet Dermatol 2021;14(5):56-58.
- Hunter J, Arentz S, Goldenberg J, et al. Zinc for the prevention or treatment of acute viral respiratory tract infections in adults: a rapid systematic review and meta-analysis of randomised controlled trials. BMJ Open. 2021;11(11):e047474. PubMed
- Yamazaki K, Kageyama H, Fujiyama T, Ito T, Urano S, Honda T. A case of systemic contact dermatitis due to zinc supplements. Int J Dermatol 2022. PubMed
- Magham K, Han J, Eilbert W, Bunney EB. Severe copper deficiency anemia caused by zinc supplement use. Am J Emerg Med 2023;72:222. PubMed
- Sivakumar RR, Chinnaiah Govindareddy D, Sahoo J, Bobby Z, Chinnakali P. Effect of daily zinc supplementation for 12 weeks on serum thyroid auto-antibody levels in children and adolescents with autoimmune thyroiditis - a randomized controlled trial. J Pedi PubMed
- AlDhasee O, AlMalki H, AlKharashi N, AlJeraisy N, Al Deeb M. Acute zinc sulfate overdose: clinical presentation and management. BMJ Case Rep 2025;18(1):e263899. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Vitamin C 51 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Back DJ, Breckenridge AM, MacIver M, et al. Interaction of ethinyloestradiol with ascorbic acid in man. Br Med J (Clin Res Ed) 1981;282:1516.
- Morris JC, Beeley L, Ballantine N. Interaction of ethinyloestradiol with ascorbic acid in man [letter]. Br Med J (Clin Res Ed) 1981;283:503.
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Dwyer JH, Merz NB, Shirocre AM, et al. Progression of early atherosclerosis and intake of vitamin C and vitamin E from supplements and food. The Los Angeles Atherosclerosis Study. 41st Annual Conference on Cardiovascular Disease Epidemiology and Prevent
- Levine M, Rumsey SC, Daruwala R, et al. Criteria and recommendations for vitamin C intake. JAMA 1999;281:1415-23. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Houston JB, Levy G. Drug biotransformation interactions in man VI: Acetaminophen and ascorbic acid. J Pharm Sci 1976;65:1218-21. PubMed
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Rosenthal G. Interaction of ascorbic acid and warfarin. JAMA 1971;215:1671. DOI
- Hume R, Johnstone JM, Weyers E. Interaction of ascorbic acid and warfarin. JAMA 1972;219:1479. DOI
- Smith EC, Skalski RJ, Johnson GC, Rossi GV. Interaction of ascorbic acid and warfarin. JAMA 1972;221:1166. DOI
- Traxer O, Huet B, Poindexter J, et al. Effect of ascorbic acid consumption on urinary stone risk factors. J Urol 2003;170:397-401.. PubMed
- Domingo JL, Gomez M, Llobet JM, Richart C. Effect of ascorbic acid on gastrointestinal aluminum absorption (letter). Lancet 1991;338:1467.
- Domingo JL, Gomez M, Llobet JM, Corbella J. Influence of some dietary constituents on aluminum absorption and retention in rats. Kidney Int 1991;39:598-601. PubMed
- Partridge NA, Regnier FE, White JL, Hem SL. Influence of dietary constituents on intestinal absorption of aluminum. Kidney Int 1989;35:1413-7. PubMed
- Mc Leod DC, Nahata MC. Inefficacy of ascorbic acid as a urinary acidifier (letter). N Engl J Med 1977;296:1413. DOI
- Hansten PD, Hayton WL. Effect of antacid and ascorbic acid on serum salicylate concentration. J Clin Pharmacol 1980;20:326-31. PubMed
- Dysken MW, Cumming RJ, Channon RA, Davis JM. Drug interaction between ascorbic acid and fluphenazine. JAMA 1979;241:2008. DOI
- Vihtamaki T, Parantainen J, Koivisto AM, et al. Oral ascorbic acid increases plasma oestradiol during postmenopausal hormone replacement therapy. Maturitas 2002;42:129-35. PubMed
- Slain D, Amsden JR, Khakoo RA, et al. Effect of high-dose vitamin C on the steady-state pharmacokinetics of the protease inhibitor indinavir in healthy volunteers. Pharmacotherapy 2005;25:165-70. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Feetam CL, Leach RH, Meynell MJ. Lack of a clinically important interaction between warfarin and ascorbic acid. Toxicol Appl Pharmacol 1975;31:544-7. PubMed
- Weintraub M, Griner PF. Warfarin and ascorbic acid: lack of evidence for a drug interaction. Toxicol Appl Pharmacol 1974;28:53-6. PubMed
- Lee DH, Folsom AR, Harnack L, et al. Does supplemental vitamin C increase cardiovascular disease risk in women with diabetes? Am J Clin Nutr 2004;80:1194-200. PubMed
- Taylor EN, Stampfer MJ, Curhan GC. Dietary factors and the risk of incident kidney stones in men: new insights after 14 years of follow-up. J Am Soc Nephrol 2004;15:3225-32. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Fairweather-Tait S, Hickson K, McGaw B, et al. Orange juice enhances aluminium absorption from antacid preparation. Eur J Clin Nutr. 1994;48(1):71-3.
- Gruenwald, J., Graubaum, H. J., Busch, R., and Bentley, C. Safety and tolerance of ester-C compared with regular ascorbic acid. Adv.Ther. 2006;23(1):171-178.
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Einerson, B., Nathorn, C., Kitiyakara, C., Sirada, M., and Thamlikitkul, V. The efficacy of ascorbic acid in suboptimal responsive anemic hemodialysis patients receiving erythropoietin: a meta-analysis. J Med.Assoc.Thai. 2011;94 Suppl 1:S134-S146.
- Li, G., Li, L., Yu, C., and Chen, L. Effect of vitamins C and E supplementation on Helicobacter pylori eradication: a meta-analysis. Br.J Nutr 2011;106(11):1632-1637.
- Chen X, Shen L, Gu X, et al. High-dose supplementation with vitamin C--induced pediatric urolithiasis: the first case report in a child and literature review. Urology. 2014;84(4):922-4. PubMed
- Sattar A, Willman JE, Kolluri R. Possible warfarin resistance due to interaction with ascorbic acid: case report and literature review. Am J Health Syst Pharm. 2013;70(9):782-6. PubMed
- Yaich S, Chaabouni Y, Charfeddine K, et al. Secondary oxalosis due to excess vitamin C intake: a cause of graft loss in a renal transplant recipient. Saudi J Kidney Dis Transpl. 2014;25(1):113-6. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Rumbold A, Ota E, Nagata C, Shahrook S, Crowther CA. Vitamin C supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004072. PubMed
- Seo MS, Kim JK, Shim JY. High-dose vitamin C promotes regression of multiple pulmonary metastases originating from hepatocellular carcinoma. Yonsei Med J. 2015;56(5):1449-52. PubMed
- Skelin M, Lucijanic T, Amidzic Klaric D, et al. Factors Affecting Gastrointestinal Absorption of Levothyroxine: A Review. Clin Ther. 2017 Feb;39(2):378-403. PubMed
- Jiang K, Tang K, Liu H, Xu H, Ye Z, Chen Z. Ascorbic acid supplements and kidney stones incidence among men and women: a systematic review and meta-analysis. Urol J. 2019;16(2):115-120.
- Thomas S, Patel D, Bittel B, et al. Effect of High-Dose Zinc and Ascorbic Acid Supplementation vs Usual Care on Symptom Length and Reduction Among Ambulatory Patients With SARS-CoV-2 Infection: The COVID A to Z Randomized Clinical Trial. JAMA Netw Open. 2 PubMed
- Giffen MA, McLemore JL. Hyperoxalosis Secondary to Intravenous Vitamin C Administration as a Non-Allopathic Treatment for Cancer. Acad Forensic Pathol 2019;9(1-2):118-126. PubMed
- Maike A, Sturgill D, Gallan A. Oxalate Nephropathy in a Renal Transplant Recipient After Receiving High Dose Ascorbic Acid. Am J Med Sci 2021. PubMed
- Shen ZY, Chen YR, Wang MC, Chang SS. High-dose vitamin C-induced acute oxalate nephropathy in a renal transplant recipient: a case report and literature review. Asian J Surg 2022. PubMed
- Yanase F, Spano S, Maeda A, et al. Mega-dose sodium ascorbate: a pilot, single-dose, physiological effect, double-blind, randomized, controlled trial. Crit Care 2023;27(1):371. PubMed
- Sharma Y, Sumanadasa S, Shahi R, et al. Efficacy and safety of vitamin C supplementation in the treatment of community-acquired pneumonia: a systematic review and meta-analysis with trial sequential analysis. Sci Rep 2024;14(1):11846. PubMed
- Pejcic AV, Petrovic NZ, Djordjic MD, Milosavljevic MN. Vitamin C Levels in Pregnant Women and the Efficacy of Vitamin C Supplements in Preventing Premature Rupture of Membranes: A Systematic Review and Meta-Analysis. Balkan Med J 2024;41(4):248-260. PubMed
Vitamin A 31 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Griffiths JK. The vitamin A paradox. J Pediatr 2000;137:604-7.. PubMed
- Hardman JG, Limbird LL, Molinoff PB, eds. Goodman and Gillman's The Pharmacological Basis of Therapeutics, 9th ed. New York, NY: McGraw-Hill, 1996.
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- FDA Talk Paper. Vitamin A and birth defects (T95-56). Food and Drug Administration, U.S. Department of Health and Human Services, Rockville, MD. October 6, 1995.
- Russell RM. The vitamin A spectrum: from deficiency to toxicity. Am J Clin Nutr 2000;71:878-84. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Feskanich D, Singh V, Willett WC, Colditz GA. Vitamin A intake and hip fractures among postmenopausal women. JAMA 2002;287:47-54. PubMed
- Melhus H, Michaelsson K, Kindmark A, et al. Excessive dietary intake of vitamin A is associated with reduced bone mineral density and increased risk for hip fracture. Ann Intern Med 1998;129:770-8. PubMed
- Michaelsson K, Lithell H, Vessby B, Melhus H. Serum retinol levels and the risk of fracture. N Engl J Med 2003;348:287-94.. PubMed
- Botterweck AA, van den Brandt PA, Goldbohm RA. Vitamins, carotenoids, dietary fiber, and the risk of gastric carcinoma: results from a prospective study after 6.3 years of follow-up. Cancer 2000;88:737-48.. DOI
- Meyskens FL Jr, Graham V, Chvapil M, et al. A phase I trial of beta-all-trans-retinoic acid delivered via a collagen sponge and a cervical cap for mild or moderate intraepithelial cervical neoplasia. J Natl Cancer Inst 1983;71:921-5..
- Hathcock JN, Hattan DG, Jenkins MY, et al. Evaluation of vitamin A toxicity. Am J Clin Nutr 1990;52:183-202.. PubMed
- Walters BN, Gubbay SS. Tetracycline and benign intracranial hypertension: report of five cases. Br Med J 1981;282:19-20.. PubMed
- Pearson MG, Littlewood SM, Bowden AN. Tetracycline and benign intracranial hypertension (letter). Br Med J 1981;282:568-9.. PubMed
- Azais-Braesco V, Pascal G. Vitamin A in pregnancy: requirements and safety limits. Am J Clin Nutr 2000;71:1325S-33S. PubMed
- Smedts HP, de Vries JH, Rakhshandehroo M, et al. High maternal vitamin E intake by diet or supplements is associated with congenital heart defects in the offspring. BJOG 2009;116:416-23. PubMed
- Grotto, I., Mimouni, M., Gdalevich, M., and Mimouni, D. Vitamin A supplementation and childhood morbidity from diarrhea and respiratory infections: a meta-analysis. J Pediatr 2003;142(3):297-304. PubMed
- Mahalanabis, D., Lahiri, M., Paul, D., Gupta, S., Gupta, A., Wahed, M. A., and Khaled, M. A. Randomized, double-blind, placebo-controlled clinical trial of the efficacy of treatment with zinc or vitamin A in infants and young children with severe acute l
- Long, K. Z., Montoya, Y., Hertzmark, E., Santos, J. I., and Rosado, J. L. A double-blind, randomized, clinical trial of the effect of vitamin A and zinc supplementation on diarrheal disease and respiratory tract infections in children in Mexico City, Mex
- Fritz, H., Kennedy, D., Fergusson, D., Fernandes, R., Doucette, S., Cooley, K., Seely, A., Sagar, S., Wong, R., and Seely, D. Vitamin A and retinoid derivatives for lung cancer: a systematic review and meta analysis. PLoS.One. 2011;6(6):e21107. PubMed
- Mayo-Wilson, E., Imdad, A., Herzer, K., Yakoob, M. Y., and Bhutta, Z. A. Vitamin A supplements for preventing mortality, illness, and blindness in children aged under 5: systematic review and meta-analysis. BMJ 2011;343:d5094. PubMed
- Mazumder S, Taneja S, Bhatia K, Yoshida S, Kaur J, Dube B, Toteja GS, Bahl R, Fontaine O, Martines J, Bhandari N; Neovita India Study Group. Efficacy of early neonatal supplementation with vitamin A to reduce mortality in infancy in Haryana, India (Neovit
- Baineni R, Gulati R, Delhi CK. Vitamin A toxicity presenting as bone pain. Arch Dis Child. 2017;102(6):556-8. PubMed
- Darlow BA, Graham PJ, Rojas-Reyes MX. Vitamin A supplementation to prevent mortality and short- and long-term morbidity in very low birth weight infants. Cochrane Database Syst Rev. 2016;(8):CD000501. PubMed
- Haider BA, Sharma R, Bhutta ZA. Neonatal vitamin A supplementation for the prevention of mortality and morbidity in term neonates in low and middle income countries. Cochrane Database Syst Rev. 2017;2:CD006980. PubMed
- Mohammad YM, Raslan IR, Al-Hussain FA. Idiopathic Intracranial Hypertension Induced by Topical Application of Vitamin A. J Neuroophthalmol. 2016;36(4):412-3. PubMed
- Masnadi Shirazi K, Nikniaz Z, Masnadi Shirazi A, Rohani M. Vitamin A supplementation decreases disease activity index in patients with ulcerative colitis: A randomized controlled clinical trial. Complement Ther Med. 2018 Dec;41:215-219. PubMed
- Ding Y, Hu P, Yang Y, et al. Impact of maternal daily oral low-dose vitamin A supplementation on the mother-infant pair: a randomised placebo-controlled trial in China. Nutrients 2021;13(7):2370. PubMed
- Knapik JJ, Hoedebecke SS. Vitamin A and bone fractures: systematic review and meta-analysis. J Spec Oper Med 2021;21(2):100-7. PubMed
- Imdad A, Mayo-Wilson E, Haykal MR, et al. Vitamin A supplementation for preventing morbidity and mortality in children from six months to five years of age. Cochrane Database Syst Rev 2022;3(3):CD008524. PubMed
Gotu Kola 18 references
- Newall CA, Anderson LA, Philpson JD. Herbal Medicine: A Guide for Healthcare Professionals. London, UK: The Pharmaceutical Press, 1996.
- Pointel JP, Boccalon H, Cloarec M, et al. Titrated extract of Centella asiatica (TECA) in the treatment of venous insufficiency of the lower limbs. Angiol 1987;38:46-50. PubMed
- Brinkhaus B, Lindner M, Schuppan D, Hahn EG. Chemical, pharmacological and clinical profile of the east Asian medical plant Centella asiatica. Phytomedicine 2000;7:427-48.
- Eun HC, Lee AY. Contact dermatitis due to madecassol. Contact Dermatitis 1985;13:310-3.. PubMed
- Hausen BM. Centella asiatica (Indian pennywort), an effective therapeutic but a weak sensitizer. Contact Dermatitis 1993;29:175-9..
- Bilbao I, Aguirre A, Zabala R, et al. Allergic contact dermatitis from butoxyethyl nicotinic acid and Centella asiatica extract. Contact Dermatitis 1995;33:435-6.
- Cesarone MR, Incandela L, De Sanctis MT, et al. Evaluation of treatment of diabetic microangiopathy with total triterpenic fraction of Centella asiatica: a clinical prospective randomized trial with a microcirculatory model. Angiology 2001;52 Suppl 2 DOI
- Bradwejn J, Zhou Y, Koszycki D, Shlik J. A double-blind, placebo-controlled study on the effects of Gotu Kola (Centella asiatica) on acoustic startle response in healthy subjects. J Clin Psychopharmacol 2000;20:680-4. PubMed
- Young GL, Jewell D. Creams for preventing stretch marks in pregnancy. Cochrane Database Syst Rev 2000;(2):CD000066. PubMed
- Jorge OA, Jorge AD. Hepatotoxicity associated with the ingestion of Centella asiatica. Rev Esp Enferm Dig 2005;97:115-24. PubMed
- Mallol J, Belda MA, Costa D, et al. Prophylaxis of striae gravidarum with a topical formulation. A double blind trial. Int J Cosmet Sci 1991;3:51-7.
- Izu, R., Aguirre, A., Gil, N., and Diaz-Perez, J. L. Allergic contact dermatitis from a cream containing Centella asiatica extract. Contact Dermatitis 1992;26(3):192-193.
- Santucci, B., Picardo, M., and Cristaudo, A. Contact dermatitis due to Centelase. Contact Dermatitis 1985;13(1):39. PubMed
- Vena, G. A. and Angelini, G. Contact allergy to Centelase. Contact Dermatitis 1986;15(2):108-109. PubMed
- Marastoni, F., Baldo, A., Redaelli, G., and Ghiringhelli, L. [Centella asiatica extract in venous pathology of the lower limbs and its evaluation as compared with tribenoside]. Minerva Cardioangiol. 1982;30(4):201-207.
- Danese, P., Carnevali, C., and Bertazzoni, M. G. Allergic contact dermatitis due to Centella asiatica extract. Contact Dermatitis 1994;31(3):201.
- Bilbao, I., Aguirre, A., Zabala, R., Gonzalez, R., Raton, J., and Diaz Perez, J. L. Allergic contact dermatitis from butoxyethyl nicotinic acid and Centella asiatica extract. Contact Dermatitis 1995;33(6):435-436.
- Dantuluri S, North-lewis P, Karthik SV. Gotu Kola induced hepatotoxicity in a child - need for caution with alternative remedies. Dig Liver Dis. 2011;43(6):500. PubMed
Pulsatilla 3 references
- Blumenthal M, ed. The Complete German Commission E Monographs: Therapeutic Guide to Herbal Medicines. Trans. S. Klein. Boston, MA: American Botanical Council, 1998.
- Newall CA, Anderson LA, Philpson JD. Herbal Medicine: A Guide for Healthcare Professionals. London, UK: The Pharmaceutical Press, 1996.
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
Echinacea 51 references
- Mullins RJ. Echinacea-associated anaphylaxis. Med J Aust 1998;168:170-1. PubMed
- Mullins RJ. Allergic reactions to Echinacea. J Allergy Clin Immunol 2000;104:S340-341 (Abstract 1003).
- Chavez ML, Chavez PI. Echinacea. Hosp Pharm 1998;33:180-8.
- Grimm W, Muller HH. A randomized controlled trial of the effect of fluid extract of Echinacea purpurea on the incidence and severity of colds and respiratory infections. Am J Med 1999;106:138-43. PubMed
- Taylor JA, Weber W, Standish L, et al. Efficacy and safety of echinacea in treating upper respiratory tract infections in children: a randomized controlled trial. JAMA 2003;290:2824-30.. PubMed
- Luettig B, Steinmuller C, Gifford GE, et al. Macrophage activation by the polysaccharide arabinogalactan isolated from plant cell cultures of Echinacea purpurea. J Natl Cancer Inst 1989;81:669-75. PubMed
- Stimpel M, Proksch A, Wagner H, et al. Macrophage activation and induction of macrophage cytotoxicity by purified polysaccharide fractions from the plant Echinacea purpurea. Infect Immun 1984;46:845-9. PubMed
- Budzinski JW, Foster BC, Vandenhoek S, Arnason JT. An in vitro evaluation of human cytochrome P450 3A4 inhibition by selected commercial herbal extracts and tinctures. Phytomedicine 2000;7:273-82. PubMed
- Gallo M, Sarkar M, Au W, et al. Pregnancy outcome following gestational exposure to echinacea: A prospective controlled study. Arch Intern Med 2000;160:3141-3. PubMed
- Soon SL, Crawford RI. Recurrent erythema nodosum associated with echinacea herbal therapy. J Am Acad Dermatol 2001;44:298-9. PubMed
- Mullins RJ, Heddle R. Adverse reactions associated with echinacea: the Australian experience. Ann Allergy Asthma Immunol 2002;88:42-51. PubMed
- Logan JL, Ahmed J. Critical hypokalemic renal tubular acidosis due to Sjogren's syndrome: association with the purported immune stimulant echinacea. Clin Rheumatol 2003;22:158-9.
- Schulten B, Bulitta M, Ballering-Bruhl B, et al. Efficacy of Echinacea purpurea in patients with a common cold. A placebo-controlled, randomised, double-blind clinical trial. Arzneimittelforschung 2001;51:563-8.. PubMed
- Yale SH, Glurich I. Analysis of the inhibitory potential of Ginkgo biloba, Echinacea purpurea, and Serenoa repens on the metabolic activity of cytochrome P450 3A4, 2D6, and 2C9. J Altern Complement Med 2005;11:433-9.
- Yale SH, Liu K. Echinacea purpurea therapy for the treatment of the common cold: a randomized, double-blind, placebo-controlled clinical trial. Arch Intern Med 2004;164:1237-41. PubMed
- Gorski JC, Huang S, Zaheer NA, et al. The effect of echinacea (Echinacea purpurea root) on cytochrome P450 activity in vivo.Clin Pharmacol Ther 2003;73 (Abstract PDII-A-8):P94. PubMed
- Lee AN, Werth VP. Activation of autoimmunity following use of immunostimulatory herbal supplements. Arch Dermatol 2004;140:723-7. PubMed
- Goel V, Lovlin R, Barton R, et al. Efficacy of a standardized echinacea preparation (Echinilin) for the treatment of the common cold: a randomized, double-blind, placebo-controlled trial. J Clin Pharm Ther 2004;29:75-83.
- Barrett B. Medicinal properties of Echinacea: a critical review. Phytomedicine 2003;10:66-86. PubMed
- Huntley AL, Thompson Coon J, Ernst E. The safety of herbal medicinal products derived from Echinacea species: a systematic review. Drug Saf 2005;28:387-400. PubMed
- Turner RB, Bauer R, Woelkart K, et al. An evaluation of Echinacea angustifolia in experimental rhinovirus infections. N Engl J Med 2005;353:341-8.
- Gurley BJ, Gardner SF, Hubbard MA, et al. In vivo assessment of botanical supplementation on human cytochrome P450 phenotypes: Citrus aurantium, Echinacea purpurea, milk thistle, and saw palmetto. Clin Pharmacol Ther 2004;76:428-40. .
- Perri D, Dugoua JJ, Mills E, Koren G. Safety and efficacy of echinacea (Echinacea augustafolia, e. purpurea and e. pallida) during pregnancy and lactation. Can J Clin Pharmacol 2006;13:e262-7.
- Kocaman O, Hulagu S, Senturk O. Echinacea-induced severe acute hepatitis with features of cholestatic autoimmune hepatitis. Eur J Intern Med 2008;19:148. PubMed
- Barrett B, Brown R, Rakel D. et al. Echinacea for treating the common cold: a randomized trial. Ann Intern Med 2010;153:769-77. PubMed
- Press Release: Echinacea herbal products should not be used in children under 12 years old. Medicines and Healthcare Products Regulatory Agency (UK). August 20, 2012. Available at: www.mhra.gov.uk/NewsCentre/Pressreleases/CON180627. (Accessed 21 October
- Barrett B, Brown R, Rakel D, Rabago D, et al. Placebo effects and the common cold: a randomized controlled trial. Ann.Fam.Med 2011;9:312-22. PubMed
- Haller J, Freund, TF, Pelczer, KG, et al. The anxiolytic potential and psychotropic side effects of an echinacea preparation in laboratory animals and healthy volunteers. Phytother.Res. 2013;27:54-61.
- Grbic J, Wexler I, Celenti R, et al. A phase II trial of a transmucosal herbal patch for the treatment of gingivitis. J Am Dent.Assoc. 2011;142:1168-75. PubMed
- Schapowal A, Berger D, Klein P, et al. Echinacea/sage or chlorhexidine/lidocaine for treating acute sore throats: a randomized double-blind trial. Eur.J Med Res 9-1-2009;14:406-12. PubMed
- Bossaer JB and Odle BL. Probable etoposide interaction with Echinacea. J.Diet.Suppl 2012;9:90-5.
- Abdul MI, Jiang X, Williams KM, et al. Pharmacokinetic and pharmacodynamic interactions of echinacea and policosanol with warfarin in healthy subjects. Br J Clin.Pharmacol. 2010;69:508-15. PubMed
- Kemp, D. E. and Franco, K. N. Possible leukopenia associated with long-term use of echinacea. J Am Board Fam.Pract. 2002;15(5):417-419.
- Liatsos, G., Elefsiniotis, I., Todorova, R., and Moulakakis, A. Severe thrombotic thrombocytopenic purpura (TTP) induced or exacerbated by the immunostimulatory herb Echinacea. Am J Hematol. 2006;81(3):224.
- Penzak, S. R., Robertson, S. M., Hunt, J. D., Chairez, C., Malati, C. Y., Alfaro, R. M., Stevenson, J. M., and Kovacs, J. A. Echinacea purpurea significantly induces cytochrome P450 3A activity but does not alter lopinavir-ritonavir exposure in healthy s
- Maskatia, Z. K. and Baker, K. Hypereosinophilia associated with echinacea use. South.Med J 2010;103(11):1173-1174. PubMed
- Parnham MJ. Benefit-risk assessment of the squeezed sap of the purple coneflower (Echinacea purpurea) for long-term oral immunostimulation. Phytomed 1996;3:95-102. PubMed
- Schroder-Aasen T, Molden G, Nilsen OG. In vitro inhibition of CYP3A4 by the multiherbal commercial product Sambucus Force and its main constituents Echinacea purpurea and Sambucus nigra. Phytother Res 2012;26(11):1606-13.
- Moltó J, Valle M, Miranda C, et al. Herb-drug interaction between Echinacea purpurea and darunavir-ritonavir in HIV-infected patients. Antimicrob Agents Chemother 2011;55(1):326-30.
- Goey AK, Meijerman I, Rosing H, et al. The effect of Echinacea purpurea on the pharmacokinetics of docetaxel. Br J Clin Pharmacol 2013;76(3):467-74.
- Moltó J, Valle M, Miranda C, et al. Herb-drug interaction between Echinacea purpurea and etravirine in HIV-infected patients. Antimicrob Agents Chemother 2012;56(10):5328-31. PubMed
- Lawrenson JA, Walls T, Day AS. Echinacea-induced acute liver failure in a child. J Paediatr Child Health 2014;50(10):841.
- Hansen TS, Nilsen OG. In vitro CYP3A4 metabolism: inhibition by Echinacea purpurea and choice of substrate for the evaluation of herbal inhibition. Basic Clin Pharmacol Toxicol 2008;103:445-9.
- Gabranis I, Koufakis T1, Papakrivos I, Batala S. Echinacea-associated acute cholestatic hepatitis. J Postgrad Med. 2015;61(3):211-2. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Karsch-Völk M, Barrett B, Kiefer D, Bauer R, Ardjomand-Woelkart K, Linde K. Echinacea for preventing and treating the common cold. Cochrane Database Syst Rev.2014;(2):CD000530. doi: 10.1002/14651858.CD000530.pub3. PubMed
- Hoban CL, Byard RW, Musgrave IF. Analysis of spontaneous adverse drug reactions to echinacea, valerian, black cohosh and ginkgo in Australia from 2000 to 2015. J Integr Med. 2019;17(5):338-343. PubMed
- Ogal M, Johnston SL, Klein P, Schoop R. Echinacea reduces antibiotic usage in children through respiratory tract infection prevention: a randomized, blinded, controlled clinical trial. Eur J Med Res. 2021 Apr 8;26(1):33. PubMed
- Lopresti AL, Smith SJ. An investigation into the anxiety-relieving and mood-enhancing effects of Echinacea angustifolia (EP107 ™): A randomised, double-blind, placebo-controlled study. J Affect Disord 2021;293:229-237.
- Weishaupt R, Buchkov A, Kolev E, Klein P, Schoop R. Reduction of viral load in patients with acute sore throats: Results from an observational clinical trial with Echinacea / Salvia lozenges [published online ahead of print, 2023 Mar 8]. Complement Med Re
- Sumer J, Keckeis K, Scanferla G, et al. Novel Echinacea formulations for the treatment of acute respiratory tract infections in adults-A randomized blinded controlled trial. Front Med (Lausanne) 2023;10:948787. PubMed
Aspartic Acid 1 reference
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Energy, Carbohydrate, Fiber, Fat, Fatty Acids, Cholesterol, Protein, and Amino Acids. Washington, DC: The National Academies Press, 2005. Available at: https://doi.org/10.17226 DOI
Saw Palmetto 22 references
- Wilt TJ, Ishani A, Stark G, et al. Saw palmetto extracts for treatment of benign prostatic hyperplasia: a systematic review. JAMA 1998;280:1604-9. PubMed
- Carraro JC, Raynaud JP, Koch G, et al. Comparison of phytotherapy (Permixon) with finasteride in the treatment of benign prostate hyperplasia: a randomized international study of 1,098 patients. Prostate 1996;29:231-40. DOI
- Di Silverio F, D'Eramo G, Lubrano C, et al. Evidence that Serenoa repens extract displays an antiestrogenic activity in prostatic tissue of benign prostatic hypertrophy patients. Eur Urol 1992;21:309-14. PubMed
- Stepanov VN, Siniakova LA, Sarrazin B, Raynaud JP. Efficacy and tolerability of the lipidosterolic extract of Serenoa repens (Permixon) in benign prostatic hyperplasia: a double-blind comparison of two dosage regimens. Adv Ther 1999;16:231-41.
- Cheema P, El-Mefty O, Jazieh AR. Intraoperative haemorrhage associated with the use of extract of Saw Palmetto herb: a case report and review of literature. J Intern Med 2001;250:167-9. PubMed
- Jibrin I, Erinle A, Saidi A, Aliyu ZY. Saw palmetto-induced pancreatitis. South Med J 2006;99:611-2. PubMed
- Prager N, Bickett K, French N, Marcovici G. A randomized, double-blind, placebo-controlled trial to determine the effectiveness of botanically derived inhibitors of 5-alpha-reductase in the treatment of androgenetic alopecia. J Altern Complement Med 2002
- Avins AL, Bent S, Staccone S, et al. A detailed safety assessment of a saw palmetto extract. Complement Ther Med 2008;16:147-54. PubMed
- Morgia, G., Mucciardi, G., Gali, A., Madonia, M., Marchese, F., Di, Benedetto A., Romano, G., Bonvissuto, G., Castelli, T., Macchione, L., and Magno, C. Treatment of chronic prostatitis/chronic pelvic pain syndrome category IIIA with Serenoa repens plus
- Aliaev, IuG, Vinarov, A. Z., Lokshin, K. L., and Spivak, L. G. [Efficiency and safety of prostamol-Uno in patients with chronic abacterial prostatitis]. Urologiia. 2006;(1):47-50.
- Agbabiaka, T. B., Pittler, M. H., Wider, B., and Ernst, E. Serenoa repens (saw palmetto): a systematic review of adverse events. Drug Saf 2009;32(8):637-647. PubMed
- Wargo, K. A., Allman, E., and Ibrahim, F. A possible case of saw palmetto-induced pancreatitis. South.Med.J. 2010;103(7):683-685. PubMed
- Lapi, F., Gallo, E., Giocaliere, E., Vietri, M., Baronti, R., Pieraccini, G., Tafi, A., Menniti-Ippolito, F., Mugelli, A., Firenzuoli, F., and Vannacci, A. Acute liver damage due to Serenoa repens: a case report. Br.J.Clin.Pharmacol. 2010;69(5):558-560.
- Mantovani, F. Serenoa repens in benign prostatic hypertrophy: analysis of 2 Italian studies. Minerva Urol.Nefrol. 2010;62(4):335-340.
- Hanaka, M., Yoshii, C., Yatera, K., Ito, C., Chojin, Y., Nagata, S., Yamasaki, K., Nishida, C., Kawanami, T., Kawanami, Y., Ishimoto, H., and Mukae, H. [A case of rhabdomyolysis caused by saw palmetto of healthy foods]. J.UOEH. 6-1-2012;34(2):193-199. PubMed
- Miroddi, M., Carni, A., Mannucci, C., Moleti, M., Navarra, M., and Calapai, G. Hot flashes in a young girl: a wake-up call concerning Serenoa repens use in children. Pediatrics 2012;130(5):e1374-e1376.
- Braeckman J. The extract of Serenoa repens in the treatment of benign prostatic hyperplasia: a multicenter open study. Current Therapeutic Research 1994;55(7):776-785. DOI
- Jipescu D, Patel A, Bohra H, Pientka A. Rare case of saw palmetto induced heart block. JACC 2017;69(11) supplement:2310.
- Morabito P, Miroddi M, Giovinazzo S, Spina E, Calapai G. Serenoa repens as an endocrine disruptor in a 10-year-Old young girl: a new case report. Pharmacology. 2015;96(1-2):41-3. doi: 10.1159/000431327.
- Gammoudi R, Ameur K, Ouni B, et al. Fixed drug eruption to Serenoa repens: first case report and consideration of the use of herbal medicine. Dermatol Ther 2020 Aug 29:e14247.
- Paulis G, Paulis A, Perletti G. Serenoa repens and its effects on male sexual function. A systematic review and meta-analysis of clinical trials. Arch Ital Urol Androl 2021;93(4):475-480. PubMed
- Venkateswaran S, Declet-Bauzo R, Shodeinde M, Gilford P. Postoperative Retroperitoneal Hematoma: A Case of Saw Palmetto and the Importance of Primary Care Intervention. HCA Healthc J Med 2020;1(5):279-282. PubMed
Sodium 38 references
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Food and Drug Administration Science Background: Safety of Sodium Phosphates Oral Solution. September 17, 2001. Available at: http://www.fda.gov/cder/drug/safety/sodiumphospate.htm
- Coton T, Mallaret C, Coilliot C, Carre D, Guisset M. Severe acute ulcerated gastritis induced by salt. Presse Med 2009;38(3):499-500. PubMed
- Frings-Meuthen P, Buehlmeier J, Baecker N, et al. High sodium chloride intake exacerbates immobilization-induced bone resorption and protein losses. J Appl Physiol 2011;111(2):537-542. PubMed
- Frings-Meuthen P, Baecker N, Heer M. Low-grade metabolic acidosis may be the cause of sodium chloride-induced exaggerated bone resorption. J Bone Miner Res 2008;23(4):517-524. PubMed
- Alam S, Johnson AG. A meta-analysis of randomised controlled trials (RCT) among healthy normotensive and essential hypertensive elderly patients to determine the effect of high salt (NaCl) diet of blood pressure. J Hum Hypertens 1999;13(6):367-74.
- Boudville N, Ward S, Benaroia M, House AA. Increased sodium intake correlates with greater use of antihypertensive agents by subjects with chronic kidney disease. Am J Hypertens 2005;18(10):1300-5. PubMed
- Bennett WM. Drug interactions and consequences of sodium restriction. Am J Clin Nutr 1997;65(2 Suppl):678S-681S. PubMed
- Okusa MD, Crystal LJ. Clinical manifestations and management of acute lithium intoxication. Am J Med 1994;97(4):383-9. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary reference intakes for water, potassium, sodium, chloride, and sulfate. Washington, DC: National Academy Press, 2005. Available at: http://www.nap.edu/openbook.php?record_id=10925. DOI
- D'Elia L, Rossi G, Ippolito R, Cappuccio FP, Strazzullo P. Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clin Nutr 2012;31(4):489-98. PubMed
- Goldsmith SR. Hyponatremia in heart failure: time for a trial. J Card Fail 2013;19(6):398-400. PubMed
- Willocks L, Brettle R, Keen J, Valentine C, Pinching AJ. Formulations of didanosine (ddI) and salt overload. Lancet 1992;339(8786):190.
- Chen L, Zhang Z, Chen W, Whelton PK, Appel LJ. Lower Sodium Intake and Risk of Headaches: Results From the Trial of Nonpharmacologic Interventions in the Elderly. Am J Public Health. 2016;106(7):1270-5. PubMed
- Cook NR, Appel LJ, Whelton PK. Lower levels of sodium intake and reduced cardiovascular risk. Circulation. 2014;129(9):981-9. PubMed
- Cook NR, Appel LJ, Whelton PK. Sodium Intake and All-Cause Mortality Over 20 Years in the Trials of Hypertension Prevention. J Am Coll Cardiol. 2016;68(15):1609-1617. PubMed
- Mente A, O'Donnell M, Rangarajan S, et al. Associations of urinary sodium excretion with cardiovascular events in individuals with and without hypertension: a pooled analysis of data from four studies. Lancet. 2016;388(10043):465-75. PubMed
- Moosavian SP, Haghighatdoost F, Surkan PJ, Azadbakht L. Salt and obesity: a systematic review and meta-analysis of observational studies. Int J Food Sci Nutr. 2017;68(3):265-277. PubMed
- O'Donnell M, Mente A, Rangarajan S, et al. Urinary sodium and potassium excretion, mortality, and cardiovascular events. N Engl J Med. 2014;371(7):612-23. DOI
- Poggio R, Gutierrez L, Matta MG, Elorriaga N, Irazola V, Rubinstein A. Daily sodium consumption and CVD mortality in the general population: systematic review and meta-analysis of prospective studies. Public Health Nutr. 2015;18(4):695-704. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Mahtani KR, Heneghan C, Onakpoya I, et al. Reduced Salt Intake for Heart Failure: A Systematic Review. JAMA Intern Med. 2018 Dec 1;178(12):1693-1700. PubMed
- Yancy CW. Sodium Restriction in Heart Failure: Too Much Uncertainty-Do the Trials. JAMA Intern Med. 2018 Dec 1;178(12):1700-1701. PubMed
- He FJ, Campbell NRC, Ma Y, MacGregor GA, Cogswell ME, Cook NR. Errors in estimating usual sodium intake by the Kawasaki formula alter its relationship with mortality: implications for public health. Int J Epidemiol. 2018;47(6):1784-1795. PubMed
- Murthy K, Ondrey GJ, Malkani N, et al. THE EFFECTS OF HYPONATREMIA ON BONE DENSITY AND FRACTURES: A SYSTEMATIC REVIEW AND META-ANALYSIS. Endocr Pract. 2019;25(4):366-378. PubMed
- Messerli FH, Hofstetter L, Syrogiannouli L, et al. Sodium intake, life expectancy, and all-cause mortality. Eur Heart J 2021;42(21):2103-2112. PubMed
- Graudal NA, Hubeck-Graudal T, Jurgens G. Effects of low sodium diet versus high sodium diet on blood pressure, renin, aldosterone, catecholamines, cholesterol, and triglyceride. Cochrane Database Syst Rev 2020;12(12):CD004022. PubMed
- Giatti S, Santos RB, Aielo AN, et al. Association of sodium with obstructive sleep apnea. The ELSA-Brasil study. Ann Am Thorac Soc 2021;18(3):502-510. PubMed
- Nan X, Lu H, Wu J, et al. The interactive association between sodium intake, alcohol consumption and hypertension among elderly in northern China: a cross-sectional study. BMC Geriatr 2021;21(1):135. PubMed
- Kyozuka H, Fukusda T, Murata T, et al. Impact of preconception sodium intake on hypertensive disorders of pregnancy: The Japan Environment and Children's study. Pregnancy Hypertens 2021;23:66-72. PubMed
- Zhao L, Ogden CL, Yang Q, et al. Association of usual sodium intake with obesity among US children and adolescents, NHANES 2009-2016. Obesity (Silver Spring) 2021;29(3):587-594. PubMed
- Ma Y, He FJ, Sun Q, et al. 24-Hour urinary sodium and potassium excretion and cardiovascular risk. N Engl J Med 2022;386(3):252-263. PubMed
- Liu J, Yang X, Zhang P, et al. Association of urinary sodium excretion and left ventricular hypertrophy in people with type 2 diabetes mellitus: A cross-sectional study. Front Endocrinol (Lausanne) 2021;12:728493. PubMed
- Filippini T, Malavolti M, Whelton PK, Vinceti M. Sodium intake and risk of hypertension: A systematic review and dose-response meta-analysis of observational cohort studies. Curr Hypertens Rep 2022;24(5):133-144. PubMed
- Wang DD, Li Y, Nguyen XT, et al. Dietary sodium and potassium intake and risk of non-fatal cardiovascular diseases: The million veteran program. Nutrients 2022;14(5):1121. PubMed
- Kwak JH, Park CH, Eun CS, et al. The associations of dietary intake of high sodium and low zinc with gastric cancer mortality: A prospective cohort study in Korea. Nutr Cancer 2022;74(10):3501-3508. PubMed
- George S, Maiti R, Mishra BR, Jena M, Mohapatra D. Effect of regulated add-on sodium chloride intake on stabilization of serum lithium concentration in bipolar disorder: A randomized controlled trial. Bipolar Disord 2023;25(1):66-75. PubMed
- Zhou TL, Schütten MTJ, Kroon AA, et al. Urinary Sodium Excretion and Salt Intake Are Not Associated With Blood Pressure Variability in a White General Population. J Am Heart Assoc 2023;12(1):e026578. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC