
Ki-HearteXX Ingredients & Drug Interactions
What is this page for?
First and foremost: checking Ki-HearteXX against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Ki-HearteXX is a dietary supplement by Viatrexx Bio Incorporated with 7 active ingredients. Its ingredients are commonly taken for diabetic nerve pain (neuropathy), blood sugar support in diabetes, antioxidant support.Based on those ingredients, 590 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Magnesium Carbonate, Alpha-Lipoic Acid, Hawthorn. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Ki-HearteXX by Viatrexx Bio Incorporated
Ask about any prescription or over-the-counter medication and we check it for interactions with Ki-HearteXX by Viatrexx Bio Incorporated — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Ki-HearteXX by Viatrexx Bio Incorporated
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Low disclosure
Ki-HearteXX contains 7 ingredients, including alpha-lipoic acid, magnesium carbonate, and three botanical extracts: foxglove, hawthorn, and lily-of-the-valley. It also includes alpha-ketoglutaric acid and a proprietary blend.
The inactive ingredients are alcohol and water. Alpha-lipoic acid is an antioxidant; magnesium supports heart and nerve function.
Foxglove and lily-of-the-valley are traditional cardiac herbs containing compounds that affect heart rhythm. Hawthorn has been studied for cardiovascular support.
The product is formulated as a liquid.
Does it work?
Moderate evidence
Our data shows alpha-lipoic acid is possibly effective for diabetic nerve pain, high cholesterol, and weight management. Magnesium is effective for indigestion and constipation.
For the botanical ingredients—foxglove, hawthorn, and lily-of-the-valley—the evidence we hold does not establish effectiveness for their traditional cardiac uses; foxglove and lily-of-the-valley show only insufficient reliable evidence, as does hawthorn for conditions like angina, heart arrhythmias, or cardiovascular disease.
How safe is it?
Well-documented data
Alpha-lipoic acid is generally well tolerated but can lower blood sugar and should be used under medical guidance. Oral side effects are typically mild—headache, heartburn, nausea—though rare cases of insulin autoimmune syndrome have been reported.
The safety data advises against alpha-lipoic acid in pregnancy and breastfeeding due to insufficient information. Magnesium is generally safe at recommended dietary amounts; at higher supplement doses, diarrhea, nausea, and vomiting can occur.
Magnesium is needed in pregnancy but should be used only under a doctor's supervision; normal dietary amounts are fine while breastfeeding. Foxglove and lily-of-the-valley are both poisonous and can cause fatal heart problems—the safety data advises against them in pregnancy and breastfeeding and warns they should never be self-used.
Hawthorn is generally well tolerated in studies but requires medical supervision for heart conditions; insufficient safety data exist for pregnancy and breastfeeding.
Meds to double-check
Major interaction found
If you take any of these, check with your pharmacist or doctor before using Ki-HearteXX: digoxin (Lanoxin) or other heart medications; blood thinners or antiplatelet drugs (like warfarin or aspirin); levodopa/carbidopa (Sinemet); muscle relaxants; water pills or diuretics; calcium channel blockers; blood-pressure medications including nitrates or ED drugs; corticosteroids; quinolone or tetracycline antibiotics; chemotherapy drugs; thyroid hormone; blood-sugar medications; lithium; or acid reducers. These represent the most serious documented interactions.
No interactions are documented for alpha-ketoglutaric acid or digitalis purpurea—we could not check them.
The bottom line
Scorecard at a glanceFormula with limited ingredient disclosure with some supporting evidence for its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
This product combines heart-supportive botanicals with magnesium and alpha-lipoic acid, but the botanical ingredients—especially foxglove and lily-of-the-valley—are potent and carry serious interaction risks with common heart and other medications. Anyone taking a prescription, particularly for the heart, blood thinning, blood pressure, Parkinson's disease, diabetes, or mental health, must check their exact medications with the tool on this page before starting.
Talk to your pharmacist or doctor first.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 5 of 7 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated May 23, 2024.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Ki-HearteXX, straight from the product label.
| Brand | Viatrexx Bio Incorporated |
|---|---|
| Barcode (UPC) | 041910305502 |
| Net contents | 1.7 Ounce(s); 50 Milliliter(s) |
| Market status | On market |
| Date entered into DSLD | May 23, 2024 |
| DSLD ID | 309872 |
| Product type | Other Combinations |
| Supplement form | Liquid |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Gluten Free, Dairy Free, Sugar Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for Ki-HearteXX by Viatrexx Bio Incorporated, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Alpha-Lipoic Acid | 0 NP | -- |
| Alpha-Ketoglutaric Acid | 0 NP | -- |
| Magnesium Carbonate | 0 NP | -- |
| Proprietary Micro Blend of Trace and Essences | 0 NP | -- |
| Foxglove | 0 NP | -- |
| Hawthorn | 0 NP | -- |
| Lily of the Valley | 0 NP | -- |
| Digitalis purpurea | 0 NP | -- |
Other ingredients: Alcohol, Water
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formulation
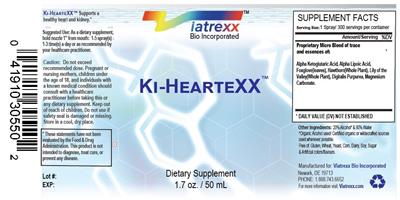
Ki-HearteXX supports a healthy heart and kidney.
Organic alcohol used/ certified organic or wildecrafted sources used whenever possible.
Free of: Gluten, wheat, yeast, corn, dairy, soy, sugar & artificial colors/flavours.
Suggested/Recommended/Usage/Directions
Suggested use: As a dietary supplement, hold nozzle 1'' from mouth: 1-5 spray(s)-1-3 time(s) a day or as recommended by your healthcare practitioner.
Precautions
Caution: Do not exceed recommended dose.
Pregnant or nursing mothers, children under the age of 18, and individuals with a known medical condition should consult with a healthcare practitioner before taking this or any dietary supplement.
Pregnant or nursing mothers, children under the age of 18, and individuals with a known medical condition should consult with a healthcare practitioner before taking this or any dietary supplement. Keep out of reach of children.
Do not use if safety seal is damaged or missing.
Storage
Store in a cool, dry place.
FDA Disclaimer Statement
These statements have not been evaluated by the Food & Drug Administration. This product is not intended to diagnose, treat cure, or prevent any disease.
FDA Statement of Identity
Dietary Supplement
General Statements
For more information visit: Viatrexx.com
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Ki-HearteXX by Viatrexx Bio Incorporated label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Ki-HearteXX by Viatrexx Bio Incorporated
These are the 7 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Spray(s) Dosage formLiquid Servings per container300 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Proprietary Micro Blend of Trace and Essences
- › Alpha-Lipoic Acid
- › Alpha-Ketoglutaric Acid
- › Magnesium Carbonate
- › Foxglove
- › Hawthorn
- › Lily of the Valley
- › Digitalis purpurea
Other (inactive) ingredients: Alcohol, Water. These complete the product’s ingredient list but are not active constituents.
Ki-HearteXX by Viatrexx Bio Incorporated Drug Interactions
HelloPharmacist Interaction Report
Ki-HearteXX by Viatrexx Bio Incorporated contains several ingredients with documented interactions with medications.
The most serious concerns involve foxglove and lily-of-the-valley, both of which contain cardiac glycosides and carry Major-severity interactions with digoxin (Lanoxin) — a heart medication — as well as with quinine and prolonged corticosteroid use. These combinations risk life-threatening heart rhythm problems and cardiac toxicity.
Read the full breakdown — every affected drug type, severity by severity
Alpha-lipoic acid carries Moderate-severity interactions with blood thinners and antiplatelet drugs (raising bleeding risk), chemotherapy drugs including alkylating agents and antitumor antibiotics (potentially reducing their effectiveness), and thyroid hormone medications (possibly decreasing their effects). Magnesium carbonate also shows Moderate interactions with muscle relaxants, potassium-sparing water pills, calcium channel blockers for blood pressure, acid-reducing medications, blood-sugar drugs (sulfonylureas), antibiotics (quinolones and bisphosphonate drugs), and notably a Major interaction with levodopa/carbidopa (Sinemet), a Parkinson's medication, where magnesium can cut drug levels by more than one-third.
Hawthorn carries Major-severity interactions with nitrates and phosphodiesterase-5 inhibitors (ED drugs like sildenafil), both of which lower blood pressure, and Moderate interactions with beta-blockers, blood thinners, and calcium channel blockers. Lily-of-the-valley adds Major interactions with corticosteroids, digoxin, and quinine, plus Moderate interactions with diuretics, lithium, stimulant laxatives, and certain antibiotics.
Alpha-ketoglutaric acid and digitalis purpurea could not be checked — we hold no interaction data for them. Altogether, these interactions span 586 individual medications.
Please use the medication checker below with your exact prescriptions before starting this product.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Ki-HearteXX?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Ki-HearteXX interact with 590 drugs. Click any drug to see the details.
5 of the 7 ingredients in Ki-HearteXX interact with drugs. Each result below shows which ingredient is responsible. Magnesium Carbonate Alpha-Lipoic Acid Hawthorn Lily of the Valley Foxglove
AvanafilStendra
How Avanafil interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
HawthornPhosphodiesterase-5 Inhibitors Major
Interaction Summary
Theoretically, concomitant use might result in additive vasodilation and hypotension.
Read the full Hawthorn + Avanafil interactionAzelastine Hydrochloride, Fluticasone PropionateDymista
How Azelastine Hydrochloride, Fluticasone Propionate interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Azelastine Hydrochloride, Fluticasone Propionate interactionBeclometasone DipropionateBecotide
How Beclometasone Dipropionate interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Beclometasone Dipropionate interactionBeclomethasoneBeclovent, Vanceril
How Beclomethasone interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Beclomethasone interactionBeclomethasone DipropionateQNASL, Qvar
How Beclomethasone Dipropionate interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Beclomethasone Dipropionate interactionBenserazide, LevodopaMadopar, Prolopa
How Benserazide, Levodopa interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Magnesium CarbonateLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium Carbonate + Benserazide, Levodopa interactionBetamethasoneCelestone, Diprolene AF, Diprosone
How Betamethasone interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Betamethasone interactionBetamethasone DipropionateSernivo
How Betamethasone Dipropionate interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Betamethasone Dipropionate interactionBetamethasone Dipropionate, CalcipotrieneEnstilar, Wynzora
How Betamethasone Dipropionate, Calcipotriene interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Betamethasone Dipropionate, Calcipotriene interactionBetamethasone ValerateLuxiq
How Betamethasone Valerate interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Betamethasone Valerate interactionBudesonideEntocort EC, Eohilia, Pulmicort, Tarpeyo, Uceris
How Budesonide interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Budesonide interactionCarbidopaLodosyn
How Carbidopa interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Magnesium CarbonateLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium Carbonate + Carbidopa interactionCarbidopa, LevodopaDhivy, Rytary, Sinemet, Sinemet CR
How Carbidopa, Levodopa interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Magnesium CarbonateLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium Carbonate + Carbidopa, Levodopa interactionCarbidopa, Levodopa, EntacaponeStalevo
How Carbidopa, Levodopa, Entacapone interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Magnesium CarbonateLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium Carbonate + Carbidopa, Levodopa, Entacapone interactionClobetasolClobex, Temovate
How Clobetasol interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Clobetasol interactionCortisone AcetateCortisone Tablets, Cortone
How Cortisone Acetate interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Cortisone Acetate interactionDexamethasoneDecadron, Dexone, Dextenza, Dexycu, Hemady, Hexadrol +1 more
How Dexamethasone interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Dexamethasone interactionDigoxinDigitek, Lanoxicaps, Lanoxin
How Digoxin interacts with Ki-HearteXX — through 4 ingredients. Tap an ingredient for the detail:
Lily Of The ValleyDigoxin (lanoxin) Major
Interaction Summary
Using lily-of-the-valley with digoxin can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Digoxin interactionFoxgloveDigoxin (lanoxin) Major
Interaction Summary
Concomitant use of digoxin is contraindicated.
Read the full Foxglove + Digoxin interactionHawthornDigoxin (lanoxin) Moderate
Interaction Summary
Theoretically, hawthorn might potentiate the effects and adverse effects of digoxin.
Read the full Hawthorn + Digoxin interactionMagnesium CarbonateDigoxin Moderate
Interaction Summary
Magnesium salts may reduce absorption of digoxin.
Read the full Magnesium Carbonate + Digoxin interactionFinasteride, TadalafilEntadfi
How Finasteride, Tadalafil interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
HawthornPhosphodiesterase-5 Inhibitors Major
Interaction Summary
Theoretically, concomitant use might result in additive vasodilation and hypotension.
Read the full Hawthorn + Finasteride, Tadalafil interactionFludrocortisoneFlorinef Acetate
How Fludrocortisone interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Fludrocortisone interactionFluticasoneFlixotide, Flonase, Flovent, Seretide, Veramyst
How Fluticasone interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Fluticasone interactionFluticasone Furoate, Umeclidinium, VilanterolTrelegy Ellipta
How Fluticasone Furoate, Umeclidinium, Vilanterol interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Fluticasone Furoate, Umeclidinium, Vilanterol interactionFluticasone Furoate, Vilanterol TrifenatateBreo Ellipta
How Fluticasone Furoate, Vilanterol Trifenatate interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Fluticasone Furoate, Vilanterol Trifenatate interactionGlyceryl TrinitrateNitronal
How Glyceryl Trinitrate interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
HawthornNitrates Major
Interaction Summary
Theoretically, concomitant use might cause additive coronary vasodilatory effects.
Read the full Hawthorn + Glyceryl Trinitrate interactionHydrocortisoneAlkindi Sprinkle, Alphaderm, Calmurid HC, Carmol HC cream, Cortef, Dioderm +8 more
How Hydrocortisone interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Lily Of The ValleyCorticosteroids Major
Interaction Summary
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Read the full Lily Of The Valley + Hydrocortisone interactionIsosorbide DinitrateAngitak, Cedocard Retard, Isoket, Isoket Retard, Isordil
How Isosorbide Dinitrate interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
HawthornNitrates Major
Interaction Summary
Theoretically, concomitant use might cause additive coronary vasodilatory effects.
Read the full Hawthorn + Isosorbide Dinitrate interactionIsosorbide Dinitrate, HydralazineBiDil
How Isosorbide Dinitrate, Hydralazine interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
HawthornNitrates Major
Interaction Summary
Theoretically, concomitant use might cause additive coronary vasodilatory effects.
Read the full Hawthorn + Isosorbide Dinitrate, Hydralazine interactionIsosorbide MononitrateAngeze, Angeze SR, Chemydur 60XL, Dynamin, Elantan, Elantan LA +13 more
How Isosorbide Mononitrate interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
HawthornNitrates Major
Interaction Summary
Theoretically, concomitant use might cause additive coronary vasodilatory effects.
Read the full Hawthorn + Isosorbide Mononitrate interactionLevodopaInbrija, Larodopa
How Levodopa interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Magnesium CarbonateLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium Carbonate + Levodopa interactionLevodopa, CarbidopaDuodopa
How Levodopa, Carbidopa interacts with Ki-HearteXX — through 1 ingredient. Tap an ingredient for the detail:
Magnesium CarbonateLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium Carbonate + Levodopa, Carbidopa interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Ki-HearteXX with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Magnesium Carbonate
Levodopa/Carbidopa (Sinemet)
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Clinical research in healthy volunteers shows that taking magnesium oxide 1000 mg with levodopa 100 mg/carbidopa 10 mg reduces the area under the curve (AUC) of levodopa by 35% and of carbidopa by 81%. In vitro and animal research shows that magnesium produces an alkaline environment in the digestive tract, which might lead to degradation and reduced bioavailability of levodopa/carbidopa.
Aminoglycoside Antibiotics
Concomitant use of aminoglycoside antibiotics and magnesium can increase the risk for neuromuscular weakness.
Both aminoglycosides and magnesium reduce presynaptic acetylcholine release, which can lead to neuromuscular blockade and possible paralysis. This is most likely to occur with high doses of magnesium given intravenously.
Antacids
Use of acid reducers may reduce the laxative effect of magnesium oxide.
A retrospective analysis shows that, in the presence of H2 receptor antagonists (H2RAs) or proton pump inhibitors (PPIs), a higher dose of magnesium oxide is needed for a laxative effect. This may also occur with antacids. Under acidic conditions, magnesium oxide is converted to magnesium chloride and then to magnesium bicarbonate, which has an osmotic laxative effect. By reducing acidity, antacids may reduce the conversion of magnesium oxide to the active bicarbonate salt.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after magnesium containing products.
Bisphosphonates
Magnesium can decrease absorption of bisphosphonates.
Cations, including magnesium, can decrease bisphosphonate absorption. Advise patients to separate doses of magnesium and these drugs by at least 2 hours.
Calcium Channel Blockers
Magnesium can have additive effects with calcium channel blockers, although evidence is conflicting.
Magnesium inhibits calcium entry into smooth muscle cells and may therefore have additive effects with calcium channel blockers. Severe hypotension and neuromuscular blockades may occur when nifedipine is used with intravenous magnesium, although some contradictory evidence suggests that concurrent use of magnesium with nifedipine does not increase the risk of neuromuscular weakness. High doses of magnesium could theoretically have additive effects with other calcium channel blockers.
Digoxin
Magnesium salts may reduce absorption of digoxin.
Clinical evidence suggests that treatment with oral magnesium hydroxide or magnesium trisilicate reduces absorption of digoxin from the intestines. This may reduce the blood levels of digoxin and decrease its therapeutic effects.
Potassium-Sparing Diuretics
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Potassium-sparing diuretics also have magnesium-sparing properties, which can counteract the magnesium losses associated with loop and thiazide diuretics. Theoretically, increased magnesium levels could result from concomitant use of potassium-sparing diuretics and magnesium supplements.
Quinolone Antibiotics
Magnesium decreases absorption of quinolones.
Magnesium can form insoluble complexes with quinolones and decrease their absorption. Advise patients to take these drugs at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Skeletal Muscle Relaxants
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Parenteral magnesium shortens the time to onset of skeletal muscle relaxants by about 1 minute and prolongs the duration of action by about 2 minutes. Magnesium potentiates the effects of skeletal muscle relaxants by decreasing calcium-mediated release of acetylcholine from presynaptic nerve terminals, reducing postsynaptic sensitivity to acetylcholine, and having a direct effect on the membrane potential of myocytes. Magnesium also has vasodilatory actions and increases cardiac output, allowing a greater amount of muscle relaxant to reach the motor end plate. A clinical study found that low-dose rocuronium (0.45 mg/kg), when given after administration of magnesium 30 mg/kg over 10 minutes, has an accelerated onset of effect, which matches the onset of effect seen with a full-dose rocuronium regimen (0.6 mg/kg). In another clinical study, onset times for rocuronium doses of 0.3, 0.6, and 1.2 mg/kg were 86, 76, and 50 seconds, respectively, when given alone, but were reduced to 66, 44, and 38 seconds, respectively, when the doses were given after a 15-minute infusion of magnesium sulfate 60 mg/kg. Giving intraoperative intravenous magnesium sulfate, 50 mg/kg loading dose followed by 15 mg/kg/hour, reduces the onset time of rocuronium, enhances its clinical effects, reduces the dose of intraoperative opiates, and prolongs the spontaneous recovery time. It does not affect the activity of subsequently administered neostigmine.
Sulfonylureas
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Clinical research shows that administration of magnesium hydroxide with glyburide increases glyburide absorption, increases maximal insulin response by 35-fold, and increases the risk of hypoglycemia, when compared with glyburide alone. A similar interaction occurs between magnesium hydroxide and glipizide. The mechanism of this effect appears to be related to the elevation of gastrointestinal pH by magnesium-based antacids, increasing solubility and enhancing absorption of sulfonylureas.
Tetracycline Antibiotics
Magnesium decreases absorption of tetracyclines.
Magnesium can form insoluble complexes with tetracyclines in the gut and decrease their absorption and antibacterial activity. Advise patients to take these drugs 1 hour before or 2 hours after magnesium supplements.
Anticoagulant/Antiplatelet Drugs
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
In vitro evidence shows that magnesium sulfate inhibits platelet aggregation, even at low concentrations. Some preliminary clinical evidence shows that infusion of magnesium sulfate increases bleeding time by 48% and reduces platelet activity. However, other clinical research shows that magnesium does not affect platelet aggregation, although inhibition of platelet-dependent thrombosis can occur.
Gabapentin (Neurontin)
Gabapentin absorption can be decreased by magnesium.
Clinical research shows that giving magnesium oxide orally along with gabapentin decreases the maximum plasma concentration of gabapentin by 33%, time to maximum concentration by 36%, and area under the curve by 43%. Advise patients to take gabapentin at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Sevelamer (Renagel, Renvela)
Sevelamer may increase serum magnesium levels.
In patients on hemodialysis, sevelamer use was associated with a 0.28 mg/dL increase in serum magnesium. The mechanism of this interaction remains unclear.
Alpha-Lipoic Acid
Alkylating Agents
Theoretically, the antioxidant effects of alpha-lipoic acid might alter the effectiveness of alkylating agents.
The use of antioxidants like alpha-lipoic acid during chemotherapy is controversial. There are concerns that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as alpha-lipoic acid have on chemotherapy. Advise patients to consult their oncologist before using alpha-lipoic acid.
Anticoagulant/Antiplatelet Drugs
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro, alpha-lipoic acid inhibits platelet aggregation.
Antitumor Antibiotics
Theoretically, the antioxidant effects of alpha-lipoic acid might alter the effectiveness of antitumor antibiotics.
The use of antioxidants like alpha-lipoic acid during chemotherapy is controversial. There are concerns that antioxidants could reduce the activity of antitumor antibiotic drugs, which work by generating free radicals. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as alpha-lipoic acid have on chemotherapy involving antitumor antibiotics. Advise patients to consult their oncologist before using alpha-lipoic acid.
Thyroid Hormone
Theoretically, alpha-lipoic acid might decrease the effects of thyroid hormone drugs.
Animal research suggests that co-administration of thyroxine with alpha-lipoic acid reduces conversion into the active T3 form.
Antidiabetes Drugs
Theoretically, taking alpha-lipoic acid with antidiabetes drugs might increase the risk of hypoglycemia.
Although some small clinical studies have suggested that alpha-lipoic acid can lower blood glucose levels, larger clinical studies in patients with diabetes have shown no clinically meaningful effect. Additionally, co-administration of single doses of alpha-lipoic acid and glyburide or acarbose did not cause detectable drug interactions in healthy volunteers.
Hawthorn
Nitrates
Theoretically, concomitant use might cause additive coronary vasodilatory effects.
Some evidence shows that hawthorn might lower blood pressure due to vasodilatory effects.
Phosphodiesterase-5 Inhibitors
Theoretically, concomitant use might result in additive vasodilation and hypotension.
Hawthorn might inhibit PDE-5 and cause vasodilation.
Anticoagulant/Antiplatelet Drugs
Theoretically, hawthorn may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro and animal research shows that hawthorn can inhibit platelet aggregation. However, its effect in humans is unclear. One observational study shows that patients taking hawthorn shortly before undergoing coronary artery bypass graft (CABG) surgery or valve replacement surgery have a 10% incidence of postoperative bleeding, compared with 1% in those who never consumed hawthorn extract. However, clinical research shows that taking a specific preparation of dried hawthorn leaves and flowers (Crataesor, Soria Natural Lab) 800 mg three times daily for 15 days does not affect platelet aggregation or levels of thromboxane B2, the metabolite of thromboxane A2, in healthy humans.
Beta-Blockers
Theoretically, concomitant use might cause additive effects on blood pressure and heart rate.
Some evidence shows that hawthorn might lower blood pressure and heart rate.
Calcium Channel Blockers
Theoretically, concomitant use might cause additive coronary vasodilation and hypotensive effects.
Some evidence shows that hawthorn might lower blood pressure due to vasodilatory effects.
Digoxin (Lanoxin)
Theoretically, hawthorn might potentiate the effects and adverse effects of digoxin.
Hawthorn appears to improve cardiac output; however, hawthorn does not appear to affect digoxin pharmacokinetics. Case reports suggest that at least one species of hawthorn root extract (Crataegus mexicana) may produce adverse effects similar to digoxin and can cross-react with digoxin assays, leading to falsely elevated plasma digoxin levels.
Lily of the Valley
Corticosteroids
Theoretically, using lily-of-the-valley with prolonged corticosteroid therapy can cause cardiac glycoside toxicity.
Lily-of-the-valley contains cardiac glycosides. Concomitant, long-term corticosteroid use can increase the risk of cardiac glycoside toxicity due to potassium depletion and electrolyte imbalance.
Digoxin (Lanoxin)
Using lily-of-the-valley with digoxin can cause cardiac glycoside toxicity.
Lily-of-the-valley contains cardiac glycosides. Use of the cardiac glycoside digoxin and lily-of-the-valley concomitantly increases the risk of cardiac glycoside toxicity.
Quinine
Theoretically, using lily-of-the-valley with quinine can increase the risk of cardiac glycoside toxicity.
Quinine may reduce the clearance of oral digoxin. Theoretically, concomitant use of quinine with lily-of-the-valley might reduce the clearance of cardiac glycosides found in lily-of-the-valley and increase the risk of toxicity.
Diuretic Drugs
Theoretically, using lily-of-the-valley with diuretics can increase the risk of cardiac glycoside toxicity.
Lily-of-the-valley contains cardiac glycosides. Concomitant use of potassium depleting diuretics and lily-of-the-valley can increase the risk of cardiac glycoside toxicity due to potassium depletion and electrolyte imbalance.
Lithium
Theoretically, lily-of-the-valley can increase levels of lithium and increase toxicity.
Lily-of-the-valley is thought to have diuretic properties. Theoretically, due to these potential diuretic effects, lily-of-the-valley might reduce excretion and increase levels of lithium. The dose of lithium might need to be decreased.
Macrolide Antibiotics
Theoretically, using lily-of-the-valley with macrolide antibiotics can increase the risk of cardiac glycoside toxicity.
Macrolide antibiotics appear to increase the gastrointestinal absorption of oral digoxin. Theoretically, concomitant use of macrolide antibiotics might increase the absorption of the cardiac glycosides found in lily-of-the-valley.
Stimulant Laxatives
Theoretically, using lily-of-the-valley with stimulant laxatives can increase the risk of cardiac glycoside toxicity.
Lily-of-the-valley contains cardiac glycosides. The overuse of stimulant laxatives can increase the risk of cardiac glycoside toxicity with lily-of-the-valley due to potassium depletion.
Tetracycline Antibiotics
Theoretically, using lily-of-the-valley with tetracycline antibiotics might increase the risk of cardiac glycoside toxicity.
Tetracycline antibiotics appear to increase the gastrointestinal absorption of oral digoxin, a cardiac glycoside. Theoretically, concomitant use of tetracycline antibiotics might increase the absorption of the cardiac glycosides found in lily-of-the-valley.
Foxglove
Digoxin (Lanoxin)
Concomitant use of digoxin is contraindicated.
Foxglove contains varied cardiac glycosides, including digoxin Taking foxglove and digoxin concomitantly increases the risk of cardiac glycoside toxicity.
Quinine
Theoretically, concomitant use of quinine increases the risk of cardiac glycoside toxicity.
Foxglove contains varied cardiac glycosides, including digoxin. Quinine can reduce the elimination of some cardiac glycosides.
Diuretic Drugs
Theoretically, concomitant use of potassium depleting diuretics increases the risk of cardiac glycoside toxicity.
Foxglove contains varied cardiac glycosides, including digoxin. Hypokalemia increases the risk of cardiac glycoside toxicity.
Macrolide Antibiotics
Theoretically, concomitant use of macrolide antibiotics increases the risk of cardiac glycoside toxicity.
Foxglove contains varied cardiac glycosides, including digoxin. Macrolide antibiotics can the reduce elimination of some cardiac glycosides.
Stimulant Laxatives
Theoretically, overuse of stimulant laxatives increases the risk of cardiac glycoside toxicity.
Foxglove contains varied cardiac glycosides, including digoxin. Hypokalemia, which may be caused by overuse of stimulant laxative, increases the risk of cardiac glycoside toxicity.
Tetracycline Antibiotics
Theoretically, concomitant use of quinine increases the risk of cardiac glycoside toxicity.
Foxglove contains varied cardiac glycosides, including digoxin. Tetracycline can increase oral absorption of some cardiac glycosides.
Brand information
Manufacturer and brand details for Ki-HearteXX, from the product label.
Viatrexx Bio Incorporated
See all Viatrexx Bio Incorporated products- Name
- Viatrexx Bio Incorporated
- City
- Newark
- State
- DE
- ZipCode
- 19713
- Phone Number
- 1.888.743.6652
- Web Address
- Viatrexx.com
Ki-HearteXX by Viatrexx Bio Incorporated: Common Questions
Does Ki-HearteXX by Viatrexx Bio Incorporated interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take this if I'm pregnant or breastfeeding?
What are the most common side effects?
Will this help my heart?
Can this lower my blood sugar?
Is this product safe if I have no medical conditions?
What's inside that makes this a liquid?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Ki-HearteXX is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Ki-HearteXX’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Alpha-lipoic Acid
Interacts with 263 drugsAlpha-lipoic acid (ALA) is an antioxidant made naturally by the body and found in small amounts in foods. It is most studied for diabetic nerve pain, where some evidence suggests it may help...
Read the full Alpha-lipoic Acid monograph → Herb & supplement monographMagnesium
Interacts with 295 drugsMagnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preventing or correcting deficiency. Some othe...
Read the full Magnesium monograph → Herb & supplement monographFoxglove
Interacts with 133 drugsFoxglove is a beautiful but highly poisonous plant that contains powerful heart-affecting compounds called cardiac glycosides. It should never be used as a home remedy or supplement because...
Read the full Foxglove monograph → Herb & supplement monographHawthorn
Interacts with 191 drugsHawthorn is a plant traditionally used for heart-related complaints, and some studies suggest it may modestly help symptoms of mild heart failure when added to standard care. However, the ev...
Read the full Hawthorn monograph → Herb & supplement monographLily-of-the-valley
Interacts with 157 drugsLily-of-the-valley is a poisonous plant that contains powerful heart-affecting compounds called cardiac glycosides, similar to the drug digoxin. While it was used historically for heart cond...
Read the full Lily-of-the-valley monograph →Sources & How We Checked
Ki-HearteXX's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 181 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Alpha-lipoic Acid 48 references
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Anon. Alpha-lipoic acid. Altern Med Rev 1998;3:308-10.
- Konrad T, Vicini P, Kusterer K, et al. Alpha-lipoic acid treatment decreases serum lactate and pyruvate concentrations and improves glucose effectiveness in lean and obese patients with Type 2 diabetes. Diabetes Care 1999;22:280-7. PubMed
- Ziegler D, Hanefeld M, Ruhnau KJ, et al. Treatment of symptomatic diabetic peripheral neuropathy with the antioxidant alpha-lipoic acid: A 3-week, multicentre randomized controlled trial (ALADIN Study). Diabetologia 1995;38:1425-33.
- Gleiter CH, Schreeb KH, Freudenthaler S, et al. Lack of interaction between thioctic acid, glibenclamide and acarbose. Br J Clin Pharmacol 1999;48:819-25. PubMed
- Jacob S, Henriksen EJ, Tritschler HJ, et al. Improvement of insulin-stimulated glucose-disposal in type 2 diabetes after repeated parenteral administration of thioctic acid. Exp Clin Endocrinol Diabet 1996;104:284-8. PubMed
- Jacob S, Henriksen EJ, Schiemann AL, et al. Enhancement of glucose disposal in patients with type 2 diabetes by alpha-lipoic acid. Arzneimittelforschung 1995;45:872-4.
- Jacob S, Ruus P, Hermann R, et al. Oral administration of RAC-alpha-lipoic acid modulates insulin sensitivity in patients with type-2 diabetes mellitus: a placebo-controlled, pilot trial. Free Rad Biol Med 1999;27:309-14.
- Segermann J, Hotze A, Ulrich H, Rao GS. Effect of alpha-lipoic acid on the peripheral conversion of thyroxine to triiodothyronine and on serum lipid-, protein- and glucose levels. Arzneimittelforschung 1991;41:1294-8.
- Beitner H. Randomized, placebo controlled, double-blind study on the clinical efficacy of a cream containing 5% alpha-lipoic acid related to photoaging of facial skin. Br J Dermatol 2003;149:841-9.
- Ziegler D, Nowak H, Kempler P, et al. Treatment of symptomatic diabetic polyneuropathy with the antioxidant alpha-lipoic acid: A meta-analysis. Diabet Med 2004;21:114-21.
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Vincent HK, Bourguignon CM, Vincent KR, Taylor AG. Effects of alpha-lipoic acid supplementation in peripheral arterial disease: a pilot study. J Alt Complement Med 2007;13:577-84. PubMed
- Furukawa N, Miyamura N, Nishida K, et al. Possible relevance of alpha lipoic acid contained in a health supplement in a case of insulin autoimmune syndrome. Diabetes Res Clin Pract 2007;75:366-7. PubMed
- Ziegler D., Ametov A., Barinov A., Dyck P. J., Gurieva I., Low P. A., Munzel U., Yakhno N., Raz I., Novosadova M., Maus J., Samigullin, R. Oral treatment with alpha-lipoic acid improves symptomatic diabetic polyneuropathy: the SYDNEY 2 trial. Diabetes Car
- Gu X. M., Zhang S. S., Wu J. C., Tang Z. Y., Lu Z. Q., Li H., Liu C., Chen L., Ning, G. [Efficacy and safety of high-dose a-lipoic acid in the treatment of diabetic polyneuropathy]. Zhonghua Yi Xue Za Zhi 2010;90(35):2473-2476.
- Porasuphatana S., Suddee S., Nartnampong A., Konsil J., Harnwong B., Santaweesuk A. Glycemic and oxidative status of patients with type 2 diabetes mellitus following oral administration of alpha-lipoic acid: a randomized double-blinded placebo-controlled
- Ansar H., Mazloom Z., Kazemi F., Hejazi N. Effect of alpha-lipoic acid on blood glucose, insulin resistance and glutathione peroxidase of type 2 diabetic patients. Saudi Med J 2011;32(6):584-588. DOI
- de Oliveira A. M., Rondó P. H., Luzia L. A., D'Abronzo F. H., Illison V. K. The effects of lipoic acid and a-tocopherol supplementation on the lipid profile and insulin sensitivity of patients with type 2 diabetes mellitus: a randomized, double-blind, pla
- Mazloom Z., Ansar H. The Effect of Alpha-Lipoic Acid on Blood Pressure in Type 2 Diabetics. Iranian Journal of Endocrinology and Metabolism 2009;11(3):245-250.
- Volchegorskii I. A., Rassokhina L. M., Koliadich M. I., Alekseev M. I. [Comparative study of alpha-lipoic acid and mexidol effects on affective status, cognitive functions and quality of life in diabetes mellitus patients]. Eksp Klin Farmakol 2011;74(11):
- Cavalcanti D. R., da Silveira F. R. Alpha lipoic acid in burning mouth syndrome--a randomized double-blind placebo-controlled trial. J Oral Pathol Med 2009;38(3):254-261. PubMed
- Koh E. H., Lee W. J., Lee S. A., Kim E. H., Cho E. H., Jeong E., Kim D. W., Kim M. S., Park J. Y., Park K. G., Lee H. J., Lee I. K., Lim S., Jang H. C., Lee K. H., Lee K. U. Effects of alpha-lipoic Acid on body weight in obese subjects. Am J Med 2011;124( PubMed
- Bergqvist-Karlsson, A., Thelin, I., and Bergendorff, O. Contact dermatitis to alpha-lipoic acid in an anti-wrinkle cream. Contact Dermatitis 2006;55(1):56-57.
- Tang, J., Wingerchuk, D. M., Crum, B. A., Rubin, D. I., and Demaerschalk, B. M. Alpha-lipoic acid may improve symptomatic diabetic polyneuropathy. Neurologist. 2007;13(3):164-167. PubMed
- Hegazy SK, Tolba OA, Mostafa TM, Eid MA, El-Afify DR. Alpha-lipoic acid improves subclinical left ventricular dysfunction in asymptomatic patients with type 1 diabetes. Rev Diabet Stud 2013;10(1):58-67. PubMed
- Huang Z, Wan X, Liu J, et al. Short-term continuous subcutaneous insulin infusion combined with insulin sensitizers rosiglitazone, metformin, or antioxidant a-lipoic acid in patients with newly diagnosed type 2 diabetes mellitus. Diabetes Technol Ther 201
- Sarezky D, Raquib AR, Dunaief JL, Kim BJ. Tolerability in the elderly population of high-dose alpha lipoic acid: a potential antioxidant therapy for the eye. Clin Ophthalmol. 2016 Sep 29;10:1899-1903. PubMed
- Boriani F, Granchi D, Roatti G, Merlini L, Sabattini T, Baldini N. Alpha-lipoic acid after median nerve decompression at the carpal tunnel: a randomized controlled trial. J Hand Surg Am. 2017 Apr;42(4):236-42. PubMed
- Karkabounas S, Papadopoulos N, Anastasiadou C, et al. Effects of a-lipoic Acid, carnosine, and thiamine supplementation in obese patients with type 2 diabetes mellitus: A randomized, double-blind study. J Med Food. 2018;21(12):1197-1203.
- Murray GL, Colombo J. (r)Alpha lipoic acid is a safe, effective pharmacologic therapy of chronic orthostatic hypotension associated with low sympathetic tone. Int J Angiol. 2019;28(3):188-193. PubMed
- Bobe G, Michels AJ, Zhang WJ, et al. A randomized controlled trial of long-term (R)-α-lipoic acid supplementation promotes weight loss in overweight or obese adults without altering baseline elevated plasma triglyceride concentrations. J Nutr. 2020:
- Passiatore M, Perna A, De-Vitis R, Taccardo G. The use of alfa-lipoic acid-R (ALA-R) in patients with mild-moderate carpal tunnel syndrome: A randomised controlled open label prospective study. Malays Orthop J. 2020;14(1):1-6. PubMed
- El-Nahas MR, Elkannishy G, Abdelhafez H, Elkhamisy ET, El-Sehrawy AA. Oral alpha lipoic acid treatment for symptomatic diabetic peripheral neuropathy: A randomized double-blinded placebo-controlled study. Endocr Metab Immune Disord Drug Targets. 2020. PubMed
- Kim BJ, Hunter A, Brucker AJ, et al. Orally administered alpha lipoic acid as a treatment for geographic atrophy: A randomized clinical trial. Ophthalmol Retina. 2020;4(9):889-898. PubMed
- Derosa G, D'Angelo A, Preti P, Maffioli P. Safety and efficacy of alpha lipoic acid during 4 years of observation: A retrospective, clinical trial in healthy subjects in primary prevention. Drug Des Devel Ther. 2020;14:5367-5374.
- Sun Y, Guan X, Wang H, et al. Randomized clinical trial of combined therapy with oral a-lipoic acid and NB-UVB for nonsegmental stable vitiligo. Dermatol Ther. 2021;34(1):e14610.
- Gilron I, Robb S, Tu D, et al. Double-blind, randomized, placebo-controlled crossover trial of alpha-lipoic acid for the treatment of fibromyalgia pain: the IMPALA trial. Pain. 2021;162(2):561-568. PubMed
- Gullo D, Evans JL, Sortino G, Goldfine ID, Vigneri R. Insulin autoimmune syndrome (Hirata Disease) in European Caucasians taking a-lipoic acid. Clin Endocrinol (Oxf). 2014;81(2):204-9.
- Yukina M, Nuralieva N, Solovyev M, Troshina E, Vasilyev E. Insulin autoimmune syndrome. Endocrinol Diabetes Metab Case Rep. 2020;2020:19-0159. PubMed
- Moffa S, Improta I, Rocchetti S, Mezza T, Giaccari A. Potential cause-effect relationship between insulin autoimmune syndrome and alpha lipoic acid: Two case reports. Nutrition. 2019;57:1-4. PubMed
- Izzo V, Greco C, Corradini D, et al. Insulin autoimmune syndrome in an Argentine woman taking a-lipoic acid: A case report and review of the literature. SAGE Open Med Case Rep. 2018;6:2050313X18819601.
- EFSA Panel on Nutrition, Novel Foods and Food Allergens (NDA), Turck D, et al. Scientific opinion on the relationship between intake of alpha-lipoic acid (thioctic acid) and the risk of insulin autoimmune syndrome. EFSA J 2021;19(6):e06577. PubMed
- Jibril AT, Jayedi A, Shab-Bidar S. Efficacy and safety of oral alpha-lipoic acid supplementation for type 2 diabetes management: a systematic review and dose-response meta-analysis of randomized trials. Endocr Connect 2022;11(10):e220322. PubMed
- Corazza M, Arlotti E, Schettini N, Pacetti L, Bianchi A, Borghi A. Allergic contact dermatitis due to a-lipoic acid in a topical over-the-counter product: A case report. Contact Dermatitis 2023.
- Velasco-Amador JP, Prados-Carmona Á, Navarro-Triviño FJ. Contact urticaria syndrome caused by alpha-lipoic acid in a master formula for vulvar lichen sclerosus. Contact Dermatitis 2023;89(2):136-137. PubMed
- Sehgal T, Ohri U, Mittal N, Attri P, Dishant F. A Case of Insulin Autoimmune Syndrome in an Indian Male Taking Alpha-Lipoic Acid. Cureus 2023;15(8):e43743. PubMed
Magnesium 82 references
- Rodin SM, Johnson BF. Pharmacokinetic interactions with digoxin. Clin Pharmacokinet 1988;15:227-44.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Dahle LO, Berg G, Hammar M, et al. The effect of oral magnesium substitution on pregnancy-induced leg cramps. Am J Obstet Gynecol 1995;173:175-80. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Peikert A, Wilimzig C, Kohne-Volland R. Prophylaxis of migraine with oral magnesium: results from a prospective, multi-center, placebo-controlled and double-blind randomized study. Cephalalgia 1996;16:257-63. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Washington, DC: National Academy Press, 1999. Available at: http://books.nap.edu/books/0309063507/html/index.html.
- Birrer RB, Shallash AJ, Totten V. Hypermagnesemia-induced fatality following epsom salt gargles. J Emerg Med 2002;22:185-8. PubMed
- Ryan MP. Diuretics and potassium/magnesium depletion. Directions for treatment. Am J Med 1987;82:38-47.. PubMed
- Hollifield JW. Magnesium depletion, diuretics, and arrhythmias. Am J Med 1987;82:30-7.. PubMed
- Heidenreich O. Mode of action of conventional and potassium-sparing diuretics--aspects with relevance to Mg-sparing effects. Magnesium 1984;3:248-56..
- Pfaffenrath V, Wessely P, Meyer C, et al. Magnesium in the prophylaxis of migraine--a double-blind placebo-controlled study. Cephalalgia 1996;16:436-40.. PubMed
- Wang F, Van Den Eeden SK, Ackerson LM, et al. Oral magnesium oxide prophylaxis of frequent migrainous headache in children: a randomized, double-blind, placebo-controlled trial. Headache 2003;43:601-10.. PubMed
- Sompolinsky D, Samra Z. Influence of magnesium and manganese on some biological and physical properties of tetracycline. J Bacteriol 1972;110:468-76.. PubMed
- Jeyabalan A, Caritis SN. Pharmacologic inhibition of preterm labor. Clin Obstet Gynecol 2002;45:99-113. PubMed
- Mittendorf R, Dambrosia J, Pryde PG, et al. Association between the use of antenatal magnesium sulfate in preterm labor and adverse health outcomes in infants. Am J Obstet Gynecol 2002;186:1111-8.. PubMed
- Witlin AG, Sibai BM. Magnesium sulfate therapy in preeclampsia and eclampsia. Obstet Gynecol 1998;92:883-9.. DOI
- Crowther CA, Hiller JE, Doyle LW. Magnesium sulphate for preventing preterm birth in threatened preterm labour. Cochrane Database Syst Rev 2002;4:CD001060. . PubMed
- Davey MJ, Teubner D. A randomized controlled trial of magnesium sulfate, in addition to usual care, for rate control in atrial fibrillation. Ann Emerg Med 2005;45:347-53.. PubMed
- L'Hommedieu CS, Nicholas D, Armes DA, et al. Potentiation of magnesium sulfate--induced neuromuscular weakness by gentamicin, tobramycin, and amikacin. J Pediatr 1983;102:629-31..
- Dunn CJ, Goa KL. Risedronate: a review of its pharmacological properties and clinical use in resorptive bone disease. Drugs 2001;61:685-712..
- Kass L, Weekes J, Carpenter L. Effect of magnesium supplementation on blood pressure: a meta-analysis. Eur J Clin Nutr 2012;66:411-8. PubMed
- Koontz SL, Friedman SA, Schwartz ML. Symptomatic hypocalcemia after tocolytic therapy with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 2004;190(6):1773-6. PubMed
- Snyder SW, Cardwell MS. Neuromuscular blockade with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 1989;161(1):35-6. PubMed
- Waisman GD, Mayorga LM, Cámera MI, et al. Magnesium plus nifedipine: potentiation of hypotensive effect in preeclampsia? Am J Obstet Gynecol. 1988;159(2):308-9. PubMed
- Brown DD, Juhl RP. Decreased bioavailability of digoxin due to antacids and kaolin-pectin. N Engl J Med. 1976;295(19):1034-7. PubMed
- Allen MD, Greenblatt DJ, Harmatz JS, et al. Effect of magnesium--aluminum hydroxide and kaolin--pectin on absorption of digoxin from tablets and capsules. J Clin Pharmacol. 1981;21(1):26-30. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an in vitro study. Thromb Haemost. 1996;76(1):88-93. DOI
- Ravn HB, Kristensen SD, Vissinger H, et al. Magnesium inhibits human platelets. Blood Coagul Fibrinolysis. 1996;7(2):241-4. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an infusion study in healthy volunteers. Thromb Haemost. 1996;75(6):939-44. DOI
- Neuvonen PJ, Kivistö KT. The effects of magnesium hydroxide on the absorption and efficacy of two glibenclamide preparations. Br J Clin Pharmacol. 1991;32(2):215-20. PubMed
- Kivistö KT, Neuvonen PJ. Enhancement of absorption and effect of glipizide by magnesium hydroxide. Clin Pharmacol Ther. 1991;49(1):39-43. PubMed
- Neuvonen PJ, Kivistö KT. Enhancement of drug absorption by antacids. An unrecognised drug interaction. Clin Pharmacokinet. 1994;27(2):120-8. PubMed
- Shechter, M., Merz, C. N., Paul-Labrador, M., Meisel, S. R., Rude, R. K., Molloy, M. D., Dwyer, J. H., Shah, P. K., and Kaul, S. Beneficial antithrombotic effects of the association of pharmacological oral magnesium therapy with aspirin in coronary heart
- Ganzevoort, J. W., Hoogerwaard, E. M., and van der Post, J. A. [Hypocalcemic delirium due to magnesium sulphate therapy in a pregnant woman with pre-eclampsia]. Ned.Tijdschr.Geneeskd. 8-3-2002;146(31):1453-1456.
- Horner, S. M. Efficacy of intravenous magnesium in acute myocardial infarction in reducing arrhythmias and mortality. Meta-analysis of magnesium in acute myocardial infarction. Circulation 1992;86(3):774-779. PubMed
- Azria, E., Tsatsaris, V., Goffinet, F., Kayem, G., Mignon, A., and Cabrol, D. [Magnesium sulfate in obstetrics: current data]. J Gynecol.Obstet.Biol.Reprod.(Paris) 2004;33(6 Pt 1):510-517.
- Magee, L. A., Miremadi, S., Li, J., Cheng, C., Ensom, M. H., Carleton, B., Cote, A. M., and von Dadelszen, P. Therapy with both magnesium sulfate and nifedipine does not increase the risk of serious magnesium-related maternal side effects in women with p
- Henyan, N. N., Gillespie, E. L., White, C. M., Kluger, J., and Coleman, C. I. Impact of intravenous magnesium on post-cardiothoracic surgery atrial fibrillation and length of hospital stay: a meta-analysis. Ann.Thorac.Surg. 2005;80(6):2402-2406. PubMed
- Li, J., Zhang, Q., Zhang, M., and Egger, M. Intravenous magnesium for acute myocardial infarction. Cochrane.Database.Syst.Rev. 2007;(2):CD002755. PubMed
- Doyle, L. W., Crowther, C. A., Middleton, P., Marret, S., and Rouse, D. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane.Database.Syst.Rev. 2009;(1):CD004661. PubMed
- Han, S., Crowther, C. A., and Moore, V. Magnesium maintenance therapy for preventing preterm birth after threatened preterm labour. Cochrane.Database.Syst.Rev. 2010;(7):CD000940. PubMed
- Duley, L., Gulmezoglu, A. M., Henderson-Smart, D. J., and Chou, D. Magnesium sulphate and other anticonvulsants for women with pre-eclampsia. Cochrane.Database.Syst.Rev. 2010;(11):CD000025. PubMed
- Conde-Agudelo, A., Romero, R., and Kusanovic, J. P. Nifedipine in the management of preterm labor: a systematic review and metaanalysis. Am J Obstet.Gynecol. 2011;204(2):134-20. PubMed
- Wong, G. K., Boet, R., Poon, W. S., Chan, M. T., Gin, T., Ng, S. C., and Zee, B. C. Intravenous magnesium sulphate for aneurysmal subarachnoid hemorrhage: an updated systemic review and meta-analysis. Crit Care 2011;15(1):R52. PubMed
- Magee, L., Sawchuck, D., Synnes, A., and von, Dadelszen P. SOGC Clinical Practice Guideline. Magnesium sulphate for fetal neuroprotection. J Obstet.Gynaecol.Can. 2011;33(5):516-529.
- Doyle, L. W. Antenatal magnesium sulfate and neuroprotection. Curr Opin Pediatr 2012;24(2):154-159. PubMed
- McDonald, S. D., Lutsiv, O., Dzaja, N., and Duley, L. A systematic review of maternal and infant outcomes following magnesium sulfate for pre-eclampsia/eclampsia in real-world use. Int J Gynaecol.Obstet. 2012;118(2):90-96. PubMed
- Gordon, M., Naidoo, K., Akobeng, A. K., and Thomas, A. G. Osmotic and stimulant laxatives for the management of childhood constipation. Cochrane.Database.Syst.Rev. 2012;7:CD009118. PubMed
- Dodd, J. M., Crowther, C. A., and Middleton, P. Oral betamimetics for maintenance therapy after threatened preterm labour. Cochrane.Database.Syst.Rev. 2012;12:CD003927. PubMed
- Wu, X., Wang, C., Zhu, J., Zhang, C., Zhang, Y., and Gao, Y. Meta-analysis of randomized controlled trials on magnesium in addition to beta-blocker for prevention of postoperative atrial arrhythmias after coronary artery bypass grafting. BMC.Cardiovasc.D PubMed
- Thorp, J. M., Jr., Katz, V. L., Campbell, D., and Cefalo, R. C. Hypersensitivity to magnesium sulfate. Am.J.Obstet.Gynecol. 1989;161(4):889-890. PubMed
- Duley L and Gulmezoglu AM. Magnesium sulphate versus lytic cocktail for eclampsia. Cochrane Database of Systematic Reviews 2000;(3) PubMed
- Gibbins KJ, Browning KR, Lopes VV, Anderson BL, Rouse DJ. Evaluation of the clinical use of magnesium sulfate for cerebral palsy prevention. Obstet Gynecol 2013;121(2 Pt 1):235-40. PubMed
- Ji D. Oral magnesium sulfate causes perforation during bowel preparation for fiberoptic colonoscopy in patients with colorectal cancer. J Emerg Med 2012;43(4):716-7. PubMed
- Yagi T, Naito T, Mino Y, Umemura K, Kawakami J. Impact of concomitant antacid administration on gabapentin plasma exposure and oral bioavailability in healthy adult subjects. Drug Metab Pharmacokinet 2012;27(2):248-54. PubMed
- Yamasaki M, Funakoshi S, Matsuda S, Imazu T, Takeda Y, Murakami T, Maeda Y. Interaction of magnesium oxide with gastric acid secretion inhibitors in clinical pharmacotherapy. Eur J Clin Pharmacol 2014;70(8):921-4. PubMed
- Choi ES, Jeong WJ, Ahn SH, Oh AY, Jeon YT, Do SH. Magnesium sulfate accelerates the onset of low-dose rocuronium in patients undergoing laryngeal microsurgery. J Clin Anesth. 2017 Feb;36:102-106. PubMed
- Ikee R, Toyoyama T, Endo T, Tsunoda M, Hashimoto N. Impact of sevelamer hydrochloride on serum magnesium concentrations in hemodialysis patients. Magnes Res. 2016 Apr 1;29(4):184-90. PubMed
- Miller ES, Sakowicz A, Leger E. Lange E, Yee LM. The association between receipt of intrapartum magnesium and postpartum hemorrhage. Am J Obstet Gynecol 2018;218(1 Suppl):S165.
- Rodríguez-Rubio L, Solis Garcia Del Pozo J, Nava E, Jordán J. Interaction between magnesium sulfate and neuromuscular blockers during the perioperative period. A systematic review and meta-analysis. J Clin Anesth. 2016;34:524-34. PubMed
- Brown RS. Magnesium Sulfate: Another Cause of a Solute Diuresis. Am J Kidney Dis. 2017;69(4):550-551. PubMed
- Park H, Qin R, Smith TJ, et al. North Central Cancer Treatment Group N10C2 (Alliance): a double-blind placebo-controlled study of magnesium supplements to reduce menopausal hot flashes. Menopause. 2015;22(6):627-32. PubMed
- Sakanoue M, Sanada J, Kanekura T. Skin eruption elicited by magnesium oxide (Maglax). J Dermatol. 2016;43(2):221-2.
- Iwamuro M, Saito S, Yoshioka M, et al. A Magnesium Oxide Bezoar. Intern Med. 2018;57(21):3087-3091. PubMed
- Vilchez G, Dai J, Kumar K, Mundy D, Kontopoulos E, Sokol RJ. Racial/ethnic disparities in magnesium sulfate neuroprotection: a subgroup analysis of a multicenter randomized controlled trial. J Matern Fetal Neonatal Med. 2018;31(17):2304-2311. PubMed
- Drug Safety Communication: FDA Recommends Against Prolonged Use of Magnesium Sulfate to Stop Pre-term Labor Due to Bone Changes in Exposed Babies. U.S. Food and Drug Administration (FDA), May 30, 2013. https://www.fda.gov/downloads/Drugs/DrugSafety/UCM353
- Committee Opinion: Magnesium Sulfate Use in Obstetrics. The American College of Obstetricians and Gynecologists Committee on Obstetric Practice Society for Maternal-Fetal Medicine, Number 652, January 2016. https://www.acog.org/Clinical-Guidance-and-Publi
- Kashihara Y, Terao Y, Yoda K, et al. Effects of magnesium oxide on pharmacokinetics of L-dopa/carbidopa and assessment of pharmacodynamic changes by a model-based simulation. Eur J Clin Pharmacol. 2019;75(3):351-361. PubMed
- Shepherd E, Salam RA, Manhas D, et al. Antenatal magnesium sulphate and adverse neonatal outcomes: A systematic review and meta-analysis. PLoS Med. 2019;16(12):e1002988. PubMed
- Hong JY, Hong JY, Choi YS, et al. Antenatal magnesium sulfate treatment and risk of necrotizing enterocolitis in preterm infants born at less than 32 weeks of gestation. Sci Rep. 2020;10(1):12826. PubMed
- Schuh S, Sweeney J, Rumantir M, et al. Effect of nebulized magnesium vs placebo added to albuterol on hospitalization among children with refractory acute asthma treated in the emergency department: a randomized clinical trial. JAMA. 2020;324(20):2038-20 PubMed
- Almeida CED, Carvalho LR, Andrade CVC, Nascimento PD Jr, Barros GAM, Modolo NSP. Effects of magnesium sulphate on the onset time of rocuronium at different doses: a randomized clinical trial. Braz J Anesthesiol. 2021;71(5):482-8. PubMed
- Gochi Valdovinos A, Arriaga-Redondo M, Dejuan Bitriá E, Pérez Rodríguez I, Márquez Isidro E, Blanco Bravo D. Prenatal therapy with magnesium sulphate and intestinal obstruction due to meconium in preterm newborns. An Pediatr (Engl Ed). 2022 Feb;96(2):138- PubMed
- Iio K, Kondo E, Shibata E, et al. Long-term tocolysis with magnesium sulfate as a risk factor for low bone mass: a case series. J Med Cases. 2022 Feb;13(2):47-50. PubMed
- Eiraku K, Uozumi Y, Hieda M, Maruyama T, Nomura H. A senile case of heart failure associated with hypermagnesemia induced by magnesium-containing laxative agent. Geriatr Gerontol Int. 2022;22(10):897-899.
- Enayati A, Gin JH, Sajeev JK, et al. Efficacy of intravenous magnesium for the management of non-post operative atrial fibrillation with rapid ventricular response: A systematic review and meta-analysis. J Cardiovasc Electrophysiol 2023;34(5):1286-1295. PubMed
- Su YH, Luo DC, Pang Y. Effects of intraoperative Magnesium sulfate infusion on emergency agitation during general anesthesia in patients undergoing radical mastectomy: a randomized controlled study. BMC Anesthesiol 2023;23(1):326. PubMed
- Han J, Park HY, Shin HJ, Chung SH, Do SH. Effects of magnesium sulphate on neostigmine-induced recovery from moderate neuromuscular blockade with rocuronium: a randomized controlled trial. Magnes Res 2023;36(2):31-39. PubMed
- Lee AT, Cordova JC, Jamplis RP, Pomicter GR. Posterior Reversible Encephalopathy Syndrome and Eclampsia in the Setting of Magnesium Toxicity: A Case Report. A A Pract 2023;17(11):e01726. PubMed
- Darmawan D, Rengganis I, Rumende CM, et al. Effectiveness and Safety of Nebulized Magnesium as Last Line Treatment in Adults with Acute Asthma Attack: A Systematic Review and Meta-Analysis. Acta Med Indones 2024;56(1):3-12.
- Shepherd ES, Goldsmith S, Doyle LW, et al. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane Database Syst Rev 2024;5(5):CD004661. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Foxglove 19 references
- Blumenthal M, ed. The Complete German Commission E Monographs: Therapeutic Guide to Herbal Medicines. Trans. S. Klein. Boston, MA: American Botanical Council, 1998.
- The Review of Natural Products by Facts and Comparisons. St. Louis, MO: Wolters Kluwer Co., 1999.
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Ellenhorn MJ, et al. Ellenhorn's Medical Toxicology: Diagnoses and Treatment of Human Poisoning. 2nd ed. Baltimore, MD: Williams & Wilkins, 1997.
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
- Gossel TA, Bricker JD. Principles of Clinical Toxicology. New York, NY:Raven Press, 1994.
- De Smet PAGM, Keller K, Hansel R, Chandler RF, Eds. Adverse Effects of Herbal Drugs 1. Verlag, Berlin: Springer, 1992. DOI
- Burnham TH, ed. Drug Facts and Comparisons, Updated Monthly. Facts and Comparisons, St. Louis, MO.
- Ramlakhan, S. L. and Fletcher, A. K. It could have happened to Van Gogh: a case of fatal purple foxglove poisoning and review of the literature. Eur.J Emerg.Med 2007;14(6):356-359. PubMed
- Yaginuma, M., Orimo, S., Kurosawa, T., Arai, M., and Hiyamuta, E. [Muscle weakness of the upper arms in the last trimester of administering digitalis]. Rinsho Shinkeigaku 1988;28(3):338-341.
- Friedman, P. L. and Smith, T. W. Foxglove and Fab: immunological approaches to digitalis intoxication. Int.J.Cardiol. 1983;3(2):237-240. PubMed
- Rich, S. A., Libera, J. M., and Locke, R. J. Treatment of foxglove extract poisoning with digoxin-specific Fab fragments. Ann.Emerg.Med 1993;22(12):1904-1907. PubMed
- Janssen RM, Berg M, Ovakim DH. Two cases of cardiac glycoside poisoning from accidental foxglove ingestion. CMAJ. 2016;188(10):747-50. PubMed
- Lin CC, Yang CC, Phua DH, Deng JF, Lu LH. An outbreak of foxglove leaf poisoning. J Chin Med Assoc. 2010;73(2):97-100. PubMed
- Wu IL, Yu JH, Lin CC, Seak CJ, Olson KR, Chen HY. Fatal cardiac glycoside poisoning due to mistaking foxglove for comfrey. Clin Toxicol (Phila). 2017:1-4. PubMed
- Negroni MS, Marengo A, Caruso D, et al. A case report of accidental intoxication following ingestion of foxglove confused with borage: High digoxinemia without major complications. Case Rep Cardiol. 2019;2019:9707428. PubMed
- Maes KR, Depuydt P, Vermassen J, De Paepe P, Buylaert W, Lyphout C. Foxglove poisoning: diagnostic and therapeutic differences with medicinal digitalis glycosides overdose. Acta Clin Belg. 2020:1-7. PubMed
- Lehmann A, Späni S, Harings-Kaim A, Probst C, Christ A, Leuppi-Taegtmeyer AB. A case of intoxication with tea made from Digitalis purpurea. Glob Cardiol Sci Pract 2021;2021(1):e202102. PubMed
- Rouault E, Ghnassia C, Filippi-Codaccioni E, Maillard N. Dose and efficacy of repeated administrations of digoxin-specific antibody fragments: Case report of foxglove poisoning. Basic Clin Pharmacol Toxicol 2021;128(1):183-186. PubMed
Hawthorn 25 references
- Tauchert M. Efficacy and safety of crataegus extract WS 1442 in comparison with placebo in patients with chronic stable New York Heart Association class-III heart failure. Am Heart J 2002;143:910-5. PubMed
- Pittler MH, Schmidt K, Ernst E. Hawthorn extract for treating chronic heart failure: meta-analysis of randomized trials. Am J Med 2003;114:665-74.. PubMed
- Chang Q, Zuo Z, Harrison F, Chow MS. Hawthorn. J Clin Pharmacol 2002;42:605-12.
- Holubarsch CJ, Colucci WS, Meinertz T, et al. The efficacy and safety of Crataegus extract WS 1442 in patients with heart failure: the SPICE trial. Eur J Heart Fail 2008;10:1255-63. PubMed
- Pittler MH, Guo R, and Ernst E. Hawthorn extract for treating chronic heart failure. Cochrane.Database.Syst Rev 2008:CD005312. PubMed
- Zick SM, Vautaw BM, Gillespie B, Aaronson KD. Hawthorn Extract Randomized Blinded Chronic Heart Failure (HERB CHF) trial. Eur J Heart Fail. 2009;11:990-99. PubMed
- Werner NS, Duschek S, and Schandry R. D-camphor-crataegus berry extract combination increases blood pressure and cognitive functioning in the elderly - a randomized, placebo controlled double blind study. Phytomedicine. 2009;16:1077-82. PubMed
- Dalli E, Colomer E, Tormos MC, et al. Crataegus laevigata decreases neutrophil elastase and has hypolipidemic effect: a randomized, double-blind, placebo-controlled trial. Phytomedicine. 6-15-2011;18:769-75. PubMed
- Maek-a-nantawat W, Phonrat B, Dhitavat J, et al. Safety and efficacy of CKBM-A01, a Chinese herbal medicine, among asymptomatic HIV patients. Southeast Asian J Trop.Med Public Health 2009;40:494-501.
- Asher GN, Viera AJ, Weaver MA, et al. Effect of hawthorn standardized extract on flow mediated dilation in prehypertensive and mildly hypertensive adults: a randomized, controlled cross-over trial. BMC.Complement Altern.Med 2012;12:26. PubMed
- Walker AF, Marakis G, Simpson E, et al. Hypotensive effects of hawthorn for patients with diabetes taking prescription drugs: a randomised controlled trial. Br J Gen.Pract 2006;56:437-43.
- Daniele C, Mazzanti G, Pittler MH, et al. Adverse-event profile of Crataegus spp.: a systematic review. Drug Saf 2006;29:523-35. PubMed
- Tankanow R, Tamer HR, Streetman DS, et al. Interaction study between digoxin and a preparation of hawthorn (Crataegus oxyacantha). J.Clin.Pharmacol. 2003;43:637-42. DOI
- Tauchert, M., Gildor, A., and Lipinski, J. [High-dose Crataegus extract WS 1442 in the treatment of NYHA stage II heart failure]. Herz 1999;24(6):465-474.
- Horoz, M., Gok, E., Genctoy, G., Ozcan, T., Olmaz, R., Akca, M., Kiykim, A., and Gurses, I. Crataegus orientalis associated multiorgan hypersensitivity reaction and acute renal failure. Intern.Med 2008;47(23):2039-2042. PubMed
- Dalli, E., Valles, J., Cosin-Sales, J., Santos, M. T., Moscardo, A., Milara, J., and Sotillo, J. F. Effects of hawthorn (Crataegus laevigata) on platelet aggregation in healthy volunteers. Thromb.Res 2011;128(4):398-400. PubMed
- Rogov VD. [Toxiderma due to the fruits of the hawthorn]. Vestn Dermatol Venerol 1984;7(7):46-47.
- Loew D, Albrecht M, and Podzuweit H. Efficacy and tolerability of a Hawthorn preparation in patients with heart failure Stage I and II according to NYHA - a surveillance study. Phytomedicine 1996;3(Suppl 1):92.
- Rababa'h AM, Altarabsheh SE, Haddad O, Deo SV, Obeidat Y, Al-Azzam S. Hawthorn Herb Increases the Risk of Bleeding after Cardiac Surgery: An Evidence-Based Approach. Heart Surg Forum 2016;19(4):E175-9. PubMed
- Shatoor AS, Soliman H, Al-Hashem F, Gamal BE, Othman A, El-Menshaw N. Effect of hawthorn (Crataegus aronia syn. Azarolus (L)) on platelet function in albino wistar rats. Thromb Res 2012;130(1):75-80. PubMed
- Vibes J, Lasserre B, Gleye J, Declume C. Inhibition of thromboxane A2 biosynthesis in vitro by the main components of Crataegus oxyacantha (hawthorn) flower heads. Prostaglandins Leukot Essent Fatty Acids 1994;50(4):173-5. PubMed
- Rogers KL, Grice ID, Griffiths LR. Inhibition of platelet aggregation and 5-HT release by extracts of Australian plants used traditionally as headache treatments. Eur J Pharm Sci 2000;9(4):355-63. PubMed
- Zhou CC, Huang XX, Gao PY, et al. Two new compounds from Crataegus pinnatifida and their antithrombotic activities. J Asian Nat Prod Res 2014;16(2):169-74.
- Palmer KG, Lebin JA, Cronin MT, Mazor SS, Burns RA. Crataegus mexicana (Tejocote) Exposure Associated with Cardiotoxicity and a Falsely Elevated Digoxin Level. J Med Toxicol. 2019;15(4):295-298. PubMed
- Espinosa J, Bassett R, Lucerna A, Finn D. Hawthorne root (Crataegus mexicana) toxicity. Am J Emerg Med. 2024;78:242.e5-242.e6. PubMed
Lily-of-the-valley 7 references
- Blumenthal M, ed. The Complete German Commission E Monographs: Therapeutic Guide to Herbal Medicines. Trans. S. Klein. Boston, MA: American Botanical Council, 1998.
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Ellenhorn MJ, et al. Ellenhorn's Medical Toxicology: Diagnoses and Treatment of Human Poisoning. 2nd ed. Baltimore, MD: Williams & Wilkins, 1997.
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
- Burnham TH, ed. Drug Facts and Comparisons, Updated Monthly. Facts and Comparisons, St. Louis, MO.
- Alexandre J, Foucault A, Coutance G, et al. Digitalis intoxication induced by an acute accidental poisoning by lily of the valley. Circulation 2012 Feb 28;125(8):1053-5. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC