
LiveXX Ingredients & Drug Interactions
What is this page for?
First and foremost: checking LiveXX against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
LiveXX is a dietary supplement by Viatrexx Bio Incorporated with 17 active ingredients. Its ingredients are commonly taken for preventing or treating thiamine deficiency, beriberi, wernicke-korsakoff syndrome (alcohol-related).Based on those ingredients, 1,561 medications have a known interaction with it, the most serious rated moderate. The ingredients most likely to interact are Milk Thistle, Niacin, Chelidonium majus. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against LiveXX by Viatrexx Bio Incorporated
Ask about any prescription or over-the-counter medication and we check it for interactions with LiveXX by Viatrexx Bio Incorporated — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of LiveXX by Viatrexx Bio Incorporated
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Low disclosure
LiveXX contains 23 ingredients in liquid form. The active ingredients include Thiamine (vitamin B1), Pyridoxine (vitamin B6), Riboflavin (vitamin B2), Vitamin B12, Niacin, Inositol, Choline Chloride, Potassium Sulfate, and Sodium Pyruvate — a blend of B vitamins and electrolytes — plus herbal extracts: Dandelion, Milk Thistle, Fringe Tree, Blessed Thistle, Ceanothus americanus (New Jersey Tea), Chelidonium majus (Greater Celandine), and Club Moss.
The formula also includes several Sus Scrofa (wild boar) ingredients and a proprietary blend. The inactive ingredients are alcohol and water.
Does it work?
Insufficient evidence
The evidence on LiveXX's overall effectiveness isn't established in our data, since the formula combines many ingredients with varying levels of support. Within it, Thiamine is effective for thiamine deficiency and Wernicke-Korsakoff syndrome (a serious brain condition from severe B1 lack) but only possibly effective for period pain and ineffective as a mosquito repellent.
Pyridoxine is effective for sideroblastic anemia and B6 deficiency, and possibly effective for pregnancy-related nausea. Riboflavin has no rated effectiveness in our data, though it's essential for energy metabolism.
Vitamin B12 is effective for B12 deficiency and certain poisonings. Inositol is possibly effective for PCOS and metabolic syndrome but possibly ineffective for anxiety and depression.
Niacin is likely effective for pellagra and possibly effective for certain HIV-related cholesterol problems. Milk Thistle is possibly effective for diabetes but has insufficient evidence for most other uses.
Dandelion, Fringe Tree, Blessed Thistle, Greater Celandine, Club Moss, and the proprietary blend lack sufficient evidence to rate. The potassium and sodium components are not rated for effectiveness.
Because this is a multi-ingredient formula with mixed evidence, you'd want to talk with a pharmacist or doctor about whether it matches your specific health goal.
How safe is it?
Well-documented data
Most of LiveXX's individual ingredients are generally well tolerated at standard doses. Thiamine, Riboflavin, and Vitamin B12 are considered very safe; excess B vitamins are cleared in your urine.
Pyridoxine is safe at normal amounts but can cause nerve damage (sensory neuropathy) with very high long-term doses — most trial participants tolerated it well, though a small number reported headache or nausea. Inositol commonly causes mild digestive upset (diarrhea, gas, nausea).
Niacin regularly causes flushing and gastrointestinal complaints, and at high prescription doses can raise liver enzymes or rarely cause liver damage. Dandelion may cause diarrhea, heartburn, or stomach discomfort; allergic reactions including anaphylaxis are rare but possible.
Milk Thistle is generally well tolerated, with mild GI symptoms most common; serious allergic reactions are rare. Choline can cause a fishy body odor and at very high doses (above its safe upper limit of 3.5 grams daily) may cause nausea, vomiting, and diarrhea.
Potassium can cause abdominal pain, nausea, vomiting, and diarrhea if taken in excess; dangerously high blood potassium is rare orally but serious. Sodium should be limited, especially if you have high blood pressure or heart disease.
Greater Celandine is concerning: it has been linked to dozens of cases of liver damage and should be avoided. Club Moss contains toxic alkaloids and has very limited safety data.
Blessed Thistle at very high doses can cause stomach irritation and vomiting. Fringe Tree, New Jersey Tea, and the Sus Scrofa ingredients have minimal human safety data.
We hold no pregnancy or breastfeeding data for Proprietary Blend, Fringe Tree, New Jersey Tea, Club Moss, Greater Celandine, or several Sus Scrofa ingredients; for the others, most are rated Likely Safe in pregnancy and lactation at recommended amounts, though some carry cautions — Pyridoxine has mixed pregnancy ratings and should not be used at high doses, Milk Thistle is best avoided in pregnancy, and Blessed Thistle is considered likely unsafe in pregnancy.
Meds to double-check
Moderate interaction found
Before taking LiveXX, have your pharmacist check it against your current medications — especially if you take blood pressure drugs (antihypertensives, ACE inhibitors, or ARBs), diabetes medications, blood thinners or antiplatelet drugs, seizure medications (phenobarbital or phenytoin), statins, the heart rhythm drug amiodarone, lithium, gout medications, acid-reflux drugs, or any drug metabolized by your liver. The formula's potassium and sodium content also matters if you take potassium-sparing diuretics, certain blood pressure drugs, or other electrolyte-sensitive medications.
No interactions are documented for the ingredients we could not check.
The bottom line
Scorecard at a glanceFormula with limited ingredient disclosure with insufficient evidence for its stated purpose. Moderate medication interactions have been identified, and safety information is well characterized.
LiveXX is a multi-ingredient supplement with both vitamins and herbal extracts, suitable for someone interested in B-vitamin and mineral support. However, several ingredients — particularly Greater Celandine, Greater Celandine — carry real safety or interaction concerns, and the formula affects many common medications.
If you take blood pressure drugs, diabetes medications, blood thinners, seizure medications, statins, or lithium, or if you have kidney disease, high potassium levels, or liver problems, you need to check this product against your exact medications first. Talk to your pharmacist or doctor before starting.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 16 of 23 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jun 20, 2024.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about LiveXX, straight from the product label.
| Brand | Viatrexx Bio Incorporated |
|---|---|
| Barcode (UPC) | 041910320505 |
| Net contents | 1.7 Ounce(s); 50 mL |
| Market status | On market |
| Date entered into DSLD | Jun 20, 2024 |
| DSLD ID | 309874 |
| Product type | Other Combinations |
| Supplement form | Liquid |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Gluten Free, Dairy Free, Sugar Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for LiveXX by Viatrexx Bio Incorporated, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Thiamine | 0 NP | -- |
| Proprietary Blend | 0 NP | -- |
| Pyridoxine | 0 NP | -- |
| Inositol | 0 NP | -- |
| Dandelion | 0 NP | -- |
| Riboflavin | 0 NP | -- |
| Vitamin B12 | 0 NP | -- |
| Milk Thistle | 0 NP | -- |
| Choline Chloride | 0 NP | -- |
| Potassium Sulfate | 0 NP | -- |
| Fringe Tree | 0 NP | -- |
| Niacin | 0 NP | -- |
| Blessed Thistle | 0 NP | -- |
| Ceanothus americanus | 0 NP | -- |
| Chelidonium majus | 0 NP | -- |
| Club Moss | 0 NP | -- |
| Sus Scrofa | 0 NP | -- |
| Sus Scrofa | 0 NP | -- |
| Sus Scrofa | 0 NP | -- |
| Sus Scrofa | 0 NP | -- |
| Sus Scrofa | 0 NP | -- |
| Sus Scrofa | 0 NP | -- |
| Sus Scrofa | 0 NP | -- |
| Sus Scrofa | 0 NP | -- |
| Sodium Pyruvate | 0 NP | -- |
Other ingredients: Alcohol, Water
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formulation
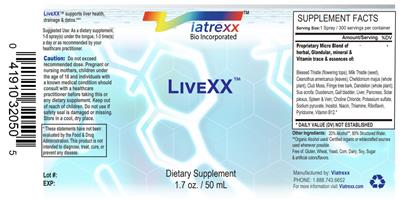
LiveXX supports liver health, drainage & detox.
Free of: Gluten, yeast, corn, dairy, soy, sugar & artificial colors/flavors.
Suggested/Recommended/Usage/Directions
Suggested use: As a dietary supplement, 1-5 spray(s) under the tongue, 1-3 time(s) a day or as recommended by your healthcare practitioner.
Precautions
Caution: Do not exceed recommended dose.
Pregnant or nursing mothers, children under the age of 18 and individuals with a known medical condition should consult with a healthcare practitioner before taking this or any dietary supplement.
Pregnant or nursing mothers, children under the age of 18 and individuals with a known medical condition should consult with a healthcare practitioner before taking this or any dietary supplement. Keep out of reach of children.
Do not use if safety seal is damaged or missing.
Storage
Store in a cool, dry place.
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure, or prevent any disease.
FDA Statement of Identity
Dietary Supplement
General Statements
For more information visit: Viatrexx.com
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
LiveXX by Viatrexx Bio Incorporated label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in LiveXX by Viatrexx Bio Incorporated
These are the 17 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Spray(s) Dosage formLiquid Servings per container300 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Proprietary Blend
- › Thiamine
- › Pyridoxine
- › Inositol
- › Dandelion
- › Riboflavin
- › Vitamin B12
- › Milk Thistle
- › Choline Chloride
- › Potassium Sulfate
- › Fringe Tree
- › Niacin
- › Blessed Thistle
- › Ceanothus americanus
- › Chelidonium majus
- › Club Moss
- › Sus Scrofa
- › Sodium Pyruvate
Other (inactive) ingredients: Alcohol, Water. These complete the product’s ingredient list but are not active constituents.
LiveXX by Viatrexx Bio Incorporated Drug Interactions
HelloPharmacist Interaction Report
LiveXX by Viatrexx Bio Incorporated is a 23-ingredient liquid supplement with documented interactions affecting multiple medication types.
The most serious interaction involves Pyridoxine (vitamin B6) with antihypertensive drugs (blood pressure medications), antiarrhythmics like amiodarone, and seizure medications — pyridoxine at high doses may reduce the effectiveness of phenobarbital and phenytoin, or potentially worsen amiodarone-related sun sensitivity.
Read the full breakdown — every affected drug type, severity by severity
Dandelion in this formula interacts with several drug categories: it may increase bleeding risk with blood thinners and antiplatelet drugs, raise potassium to unsafe levels with potassium-sparing diuretics (water pills that preserve potassium), lower blood sugar with diabetes medications, affect how your body clears certain antibiotics (quinolones like ciprofloxacin), and theoretically alter lithium levels through its diuretic action. Milk thistle carries Moderate interactions with diabetes drugs, blood thinners like warfarin, certain heart and transplant medications, and drugs metabolized through specific liver pathways.
Inositol and Potassium Sulfate both interact with diabetes medications and potassium-sparing diuretics or ACE inhibitors/ARBs (blood pressure drugs), raising the risk of low blood sugar or dangerously high potassium. Niacin at high doses affects antihypertensives, statins (cholesterol drugs), diabetes medications, and gout drugs.
Chelidonium majus (greater celandine) carries concerns with certain antidepressants and drugs metabolized by CYP2D6, as well as liver-toxic drugs. Lesser interactions involve Thiamine with the antibiotic trimethoprim, Choline with atropine, Blessed Thistle with acid-reflux medications, and Club Moss with cholinergic or anticholinergic drugs.
Altogether, these interactions span 1,538 individual medications.
Sodium Pyruvate and Vitamin B12 (with metformin) round out the documented concerns. We could not check several Sus Scrofa ingredients — we hold no data for them.
Use the medication checker below with your exact drugs before starting.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against LiveXX?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in LiveXX interact with 1,561 drugs. Click any drug to see the details.
14 of the 17 ingredients in LiveXX interact with drugs. Each result below shows which ingredient is responsible. Milk Thistle Niacin Chelidonium majus Dandelion Club Moss Pyridoxine Sodium Pyruvate Inositol Potassium Sulfate Blessed Thistle Riboflavin Vitamin B12 Choline Chloride Thiamine
6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with LiveXX — through 2 ingredients. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + 6-mercaptopurine interactionChelidonium MajusImmunosuppressants, Hepatotoxic Drugs Moderate
Interaction Summary
Preliminary clinical research suggests that taking a specific semi-synthetic derivative of the greater celandine constituent chelidonine (Ukrain; not available in North America) might stimulate immune responses in cancer patients.
Read the full Chelidonium Majus + 6-mercaptopurine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with LiveXX — through 2 ingredients. Tap an ingredient for the detail:
Chelidonium MajusHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Abacavir Sulfate, Dolutegravir, Lamivudine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with LiveXX — through 2 ingredients. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Abacavir, Lamivudine interactionChelidonium MajusHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Abacavir, Lamivudine interactionAbciximabReoPro
How Abciximab interacts with LiveXX — through 2 ingredients. Tap an ingredient for the detail:
DandelionAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
Read the full Dandelion + Abciximab interactionNiacinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Niacin + Abciximab interactionAbiraterone
How Abiraterone interacts with LiveXX — through 3 ingredients. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Abiraterone interactionChelidonium MajusHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Abiraterone interactionMilk ThistleCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with LiveXX — through 3 ingredients. Tap an ingredient for the detail:
Chelidonium MajusHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Abiraterone Acetate interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Abiraterone Acetate interactionMilk ThistleCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with LiveXX — through 4 ingredients. Tap an ingredient for the detail:
NiacinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Niacin + Abrocitinib interactionChelidonium MajusImmunosuppressants Moderate
Interaction Summary
Preliminary clinical research suggests that taking a specific semi-synthetic derivative of the greater celandine constituent chelidonine (Ukrain; not available in North America) might stimulate immune responses in cancer patients.
Read the full Chelidonium Majus + Abrocitinib interactionDandelionAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
Read the full Dandelion + Abrocitinib interactionMilk ThistleCytochrome P450 2c9 (cyp2c9) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP2C9; research is conflicting.
Read the full Milk Thistle + Abrocitinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with LiveXX — through 5 ingredients. Tap an ingredient for the detail:
Milk ThistleAntidiabetes Drugs Moderate
Interaction Summary
Taking milk thistle with antidiabetes drugs may increase the risk of hypoglycemia.
Read the full Milk Thistle + Acarbose interactionNiacinAntidiabetes Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Niacin can increase blood glucose levels and may diminish the effects of antidiabetes drugs.
Read the full Niacin + Acarbose interactionDandelionAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase the risk for hypoglycemia when used with antidiabetes drugs.
Read the full Dandelion + Acarbose interactionInositolAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking inositol with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Inositol + Acarbose interactionChelidonium MajusHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with LiveXX — through 4 ingredients. Tap an ingredient for the detail:
Chelidonium MajusHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acebutolol interactionNiacinAntihypertensive Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
Read the full Niacin + Acebutolol interactionPyridoxineAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Pyridoxine + Acebutolol interactionSodium PyruvateAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium Pyruvate + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with LiveXX — through 2 ingredients. Tap an ingredient for the detail:
NiacinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Niacin + Acenocoumarol interactionDandelionAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
Read the full Dandelion + Acenocoumarol interactionAcepromazineAtravet
How Acepromazine interacts with LiveXX — through 1 ingredient. Tap an ingredient for the detail:
Club MossAnticholinergic Drugs Moderate
Interaction Summary
Evidence from in vitro research suggests that clubmoss extract can inhibit acetylcholinesterase activity.
Read the full Club Moss + Acepromazine interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with LiveXX — through 4 ingredients. Tap an ingredient for the detail:
Milk ThistleGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen interactionDandelionGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion + Acetaminophen interactionChelidonium MajusHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acetaminophen interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with LiveXX — through 4 ingredients. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs, Aspirin +1 Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Aspirin interactionMilk ThistleGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen, Aspirin interactionDandelionCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion + Acetaminophen, Aspirin interactionChelidonium MajusHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with LiveXX — through 4 ingredients. Tap an ingredient for the detail:
DandelionGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion + Acetaminophen, Aspirin, Caffeine interactionChelidonium MajusHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acetaminophen, Aspirin, Caffeine interactionNiacinAnticoagulant/antiplatelet Drugs, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Niacin + Acetaminophen, Aspirin, Caffeine interactionMilk ThistleGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with LiveXX — through 4 ingredients. Tap an ingredient for the detail:
Milk ThistleGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionDandelionGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionChelidonium MajusHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, ButalbitalAxocet, Bancap, Bucet, Butex Forte, Esgic CF, Orbivan CF +5 more
How Acetaminophen, Butalbital interacts with LiveXX — through 4 ingredients. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital interactionMilk ThistleGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen, Butalbital interactionDandelionCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion + Acetaminophen, Butalbital interactionChelidonium MajusHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acetaminophen, Butalbital interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with LiveXX — through 4 ingredients. Tap an ingredient for the detail:
DandelionGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion + Acetaminophen, Butalbital, Caffeine interactionChelidonium MajusHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acetaminophen, Butalbital, Caffeine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital, Caffeine interactionMilk ThistleGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with LiveXX — through 4 ingredients. Tap an ingredient for the detail:
Milk ThistleCytochrome P450 3a4 (cyp3a4) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle + Acetaminophen, Butalbital, Caffeine, Codeine interactionDandelionCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion + Acetaminophen, Butalbital, Caffeine, Codeine interactionChelidonium MajusHepatotoxic Drugs, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acetaminophen, Butalbital, Caffeine, Codeine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with LiveXX — through 4 ingredients. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital, Codeine interactionMilk ThistleGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen, Butalbital, Codeine interactionChelidonium MajusCytochrome P450 2d6 (cyp2d6) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Research in vitro shows that chelidonine, a constituent of greater celandine, inhibits cytochrome P450 2D6 (CYP2D6) enzyme activity.
Read the full Chelidonium Majus + Acetaminophen, Butalbital, Codeine interactionDandelionCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with LiveXX — through 4 ingredients. Tap an ingredient for the detail:
Chelidonium MajusHepatotoxic Drugs, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acetaminophen, Butalbital, Codeine Phosphate interactionDandelionGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion + Acetaminophen, Butalbital, Codeine Phosphate interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital, Codeine Phosphate interactionMilk ThistleGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with LiveXX — through 5 ingredients. Tap an ingredient for the detail:
Milk ThistleGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionClub MossAnticholinergic Drugs Moderate
Interaction Summary
Evidence from in vitro research suggests that clubmoss extract can inhibit acetylcholinesterase activity.
Read the full Club Moss + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionChelidonium MajusHepatotoxic Drugs, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionDandelionGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with LiveXX — through 4 ingredients. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Caffeine, Codeine interactionMilk ThistleGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen, Caffeine, Codeine interactionDandelionCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion + Acetaminophen, Caffeine, Codeine interactionChelidonium MajusCytochrome P450 2d6 (cyp2d6) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Research in vitro shows that chelidonine, a constituent of greater celandine, inhibits cytochrome P450 2D6 (CYP2D6) enzyme activity.
Read the full Chelidonium Majus + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with LiveXX — through 4 ingredients. Tap an ingredient for the detail:
DandelionGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion + Acetaminophen, Caffeine, Codeine, Salicylamide interactionChelidonium MajusHepatotoxic Drugs, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acetaminophen, Caffeine, Codeine, Salicylamide interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Caffeine, Codeine, Salicylamide interactionMilk ThistleGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with LiveXX — through 4 ingredients. Tap an ingredient for the detail:
Milk ThistleGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen, Caffeine, Dihydrocodeine interactionChelidonium MajusCytochrome P450 2d6 (cyp2d6) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Research in vitro shows that chelidonine, a constituent of greater celandine, inhibits cytochrome P450 2D6 (CYP2D6) enzyme activity.
Read the full Chelidonium Majus + Acetaminophen, Caffeine, Dihydrocodeine interactionDandelionGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion + Acetaminophen, Caffeine, Dihydrocodeine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Caffeine, IsomethepteneMigralam
How Acetaminophen, Caffeine, Isometheptene interacts with LiveXX — through 4 ingredients. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Caffeine, Isometheptene interactionMilk ThistleCytochrome P450 3a4 (cyp3a4) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle + Acetaminophen, Caffeine, Isometheptene interactionDandelionCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion + Acetaminophen, Caffeine, Isometheptene interactionChelidonium MajusHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acetaminophen, Caffeine, Isometheptene interactionAcetaminophen, Caffeine, PyrilamineMidol Max Strength Menstrual
How Acetaminophen, Caffeine, Pyrilamine interacts with LiveXX — through 5 ingredients. Tap an ingredient for the detail:
DandelionGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion + Acetaminophen, Caffeine, Pyrilamine interactionChelidonium MajusHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acetaminophen, Caffeine, Pyrilamine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Caffeine, Pyrilamine interactionMilk ThistleGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen, Caffeine, Pyrilamine interactionClub MossAnticholinergic Drugs Moderate
Interaction Summary
Evidence from in vitro research suggests that clubmoss extract can inhibit acetylcholinesterase activity.
Read the full Club Moss + Acetaminophen, Caffeine, Pyrilamine interactionAcetaminophen, Chlorpheniramine Maleate, Dextromethorphan HbrVicks Formula 44M Cough, Cold & Flu Relief
How Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interacts with LiveXX — through 5 ingredients. Tap an ingredient for the detail:
Milk ThistleGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionClub MossAnticholinergic Drugs Moderate
Interaction Summary
Evidence from in vitro research suggests that clubmoss extract can inhibit acetylcholinesterase activity.
Read the full Club Moss + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionChelidonium MajusHepatotoxic Drugs, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionDandelionGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with LiveXX — through 5 ingredients. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionClub MossAnticholinergic Drugs Moderate
Interaction Summary
Evidence from in vitro research suggests that clubmoss extract can inhibit acetylcholinesterase activity.
Read the full Club Moss + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionMilk ThistleGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionDandelionCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionChelidonium MajusCytochrome P450 2d6 (cyp2d6) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Research in vitro shows that chelidonine, a constituent of greater celandine, inhibits cytochrome P450 2D6 (CYP2D6) enzyme activity.
Read the full Chelidonium Majus + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionAcetaminophen, Chlorpheniramine, DextromethorphanCoricidin II Extra Strength Cold and Flu
How Acetaminophen, Chlorpheniramine, Dextromethorphan interacts with LiveXX — through 5 ingredients. Tap an ingredient for the detail:
Chelidonium MajusCytochrome P450 2d6 (cyp2d6) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Research in vitro shows that chelidonine, a constituent of greater celandine, inhibits cytochrome P450 2D6 (CYP2D6) enzyme activity.
Read the full Chelidonium Majus + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionDandelionCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionMilk ThistleGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionClub MossAnticholinergic Drugs Moderate
Interaction Summary
Evidence from in vitro research suggests that clubmoss extract can inhibit acetylcholinesterase activity.
Read the full Club Moss + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionAcetaminophen, Chlorpheniramine, Dextromethorphan HydrobromideCoricidin HBP Maximum Strength Flu
How Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interacts with LiveXX — through 5 ingredients. Tap an ingredient for the detail:
Club MossAnticholinergic Drugs Moderate
Interaction Summary
Evidence from in vitro research suggests that clubmoss extract can inhibit acetylcholinesterase activity.
Read the full Club Moss + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionMilk ThistleCytochrome P450 3a4 (cyp3a4) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionChelidonium MajusHepatotoxic Drugs, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Chelidonium Majus + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionDandelionGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionEach ingredient & the kinds of drugs it affects
For each ingredient in LiveXX with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Milk Thistle
Antidiabetes Drugs
Taking milk thistle with antidiabetes drugs may increase the risk of hypoglycemia.
Clinical research shows that milk thistle extract, alone or along with tree turmeric extract, can lower blood glucose levels and glycated hemoglobin (HbA1c) in patients with type 2 diabetes, including those already taking antidiabetes drugs. Additionally, animal research shows that milk thistle extract increases the metformin maximum plasma concentration and area under the curve and decreases the renal clearance of metformin, due to inhibition of the multi-drug and toxin extrusion protein 1 (MATE1) renal tubular transport protein.
Cytochrome P450 2B6 (Cyp2B6) Substrates
Theoretically, milk thistle might inhibit CYP2B6.
An in vitro study shows that silybin, a constituent of milk thistle, binds to and noncompetitively inhibits CYP2B6. Additionally, silybin might downregulate the expression of CYP2B6 by decreasing mRNA and protein levels.
Glucuronidated Drugs
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Laboratory research shows that milk thistle constituents inhibit uridine diphosphoglucuronosyl transferase (UGT), the major phase 2 enzyme that is responsible for glucuronidation. Theoretically, this could decrease the clearance and increase levels of glucuronidated drugs. Other laboratory research suggests that a milk thistle extract of silymarin might inhibit beta-glucuronidase, although the significance of this effect is unclear.
Ledipasvir
Theoretically, milk thistle might increase the levels and clinical effects of ledipasvir.
Animal research in rats shows that milk thistle increases the area under the curve (AUC) for ledipasvir and slows its elimination.
Morphine
Theoretically, concomitant use of milk thistle with morphine might affect serum levels of morphine and either increase or decrease its effects.
Animal research shows that milk thistle reduces serum levels of morphine by up to 66%. In contrast, laboratory research shows that milk thistle constituents inhibit uridine diphosphoglucuronosyl transferase (UGT), the major phase 2 enzyme that is responsible for glucuronidation. Theoretically, this could decrease the clearance and increase morphine levels. The effect of taking milk thistle on morphine metabolism in humans is not known.
Raloxifene (Evista)
Theoretically, milk thistle might decrease the clearance and increase levels of raloxifene.
Laboratory research suggests that the milk thistle constituents silibinin and silymarin inhibit the glucuronidation of raloxifene in the intestines.
Sirolimus (Rapamune)
Milk thistle might decrease the clearance of sirolimus.
Pharmacokinetic research shows that a milk thistle extract of silymarin decreases the apparent clearance of sirolimus in hepatically impaired renal transplant patients. It is unclear if this interaction occurs in patients without hepatic impairment.
Sofosbuvir (Solvaldi)
Theoretically, milk thistle might decrease the levels and clinical effects of sofosbuvir.
Animal research in rats shows that milk thistle reduces the metabolism of sofosbuvir, as well as the hepatic uptake of its active metabolite.
Tamoxifen (Nolvadex)
Theoretically, the milk thistle constituent silibinin might increase tamoxifen levels and interfere with its conversion to an active metabolite.
Animal research suggests that the milk thistle constituent silibinin might increase plasma levels of tamoxifen and alter its conversion to an active metabolite. The mechanism appears to involve inhibition of pre-systemic metabolism of tamoxifen by cytochrome P450 (CYP) 2C9 and CYP3A4, and inhibition of P-glycoprotein-mediated efflux of tamoxifen into the intestine for excretion. Whether this interaction occurs in humans is not known.
Warfarin (Coumadin)
Theoretically, milk thistle might increase the effects of warfarin.
In one case report, a man stabilized on warfarin experienced an increase in INR from 2.64 to 4.12 after taking a combination product containing milk thistle 200 mg daily, as well as dandelion, wild yam, niacinamide, and vitamin B12. Levels returned to normal after stopping the supplement. Although a direct correlation between milk thistle and the change in INR cannot be confirmed, some in vitro research suggests that milk thistle might inhibit cytochrome P450 2C9 (CYP2C9), an enzyme involved in the metabolism of various drugs, including warfarin.
Cytochrome P450 2C9 (Cyp2C9) Substrates
It is unclear if milk thistle inhibits CYP2C9; research is conflicting.
In vitro research suggests that milk thistle might inhibit CYP2C9. Additionally, 3 case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking milk thistle and cancer medications that are CYP2C9 substrates, including imatinib and capecitabine. However, contradictory clinical research shows that milk thistle extract does not inhibit CYP2C9 or significantly affect levels of the CYP2C9 substrate tolbutamide. Differences in results could be due to differences in dosages or formulations utilized.
Cytochrome P450 3A4 (Cyp3A4) Substrates
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
While laboratory research shows conflicting results, pharmacokinetic research shows that taking milk thistle extract 420-1350 mg daily does not significantly affect the metabolism of the CYP3A4 substrates irinotecan, midazolam, or indinavir. However, 8 case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking milk thistle and cancer medications that are CYP3A4 substrates, including gefitinib, sorafenib, doxorubicin, and vincristine.
Estrogens
Theoretically, milk thistle might interfere with estrogen therapy through competition for estrogen receptors.
Animal research suggests that a milk thistle extract of silymarin binds to estrogen receptor beta.
Hmg-Coa Reductase Inhibitors ("Statins")
Theoretically, milk thistle might interfere with statin therapy by decreasing the activity of organic anion transporting polypeptide 1B1 (OATB1B1) and inhibiting breast cancer resistance protein (BCRP).
Preliminary evidence suggests that a milk thistle extract of silymarin can decrease the activity of the OATP1B1, which transports HMG-CoA reductase inhibitors into the liver to their site of action, and animal research shows this increases the maximum plasma concentration of pitavastatin and pravastatin. The silibinin component also inhibits BCRP, which transports statins from the liver into the bile for excretion. However, in a preliminary study in healthy males, silymarin 140 mg three times daily had no effect on the pharmacokinetics of a single 10 mg dose of rosuvastatin.
Indinavir (Crixivan)
Theoretically, milk thistle may induce cytochrome P450 3A4 (CYP3A4) enzymes and increase the metabolism of indinavir; however, results are conflicting.
One pharmacokinetic study shows that taking milk thistle (Standardized Milk Thistle, General Nutrition Corp.) 175 mg three times daily in combination with multiple doses of indinavir 800 mg every 8 hours decreases the mean trough levels of indinavir by 25%. However, results from the same pharmacokinetic study show that milk thistle does not affect the overall exposure to indinavir. Furthermore, two other pharmacokinetic studies show that taking specific milk thistle extract (Legalon, Rottapharm Madaus; Thisilyn, Nature's Way) 160-450 mg every 8 hours in combination with multiple doses of indinavir 800 mg every 8 hours does not reduce levels of indinavir.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Milk thistle may inhibit one form of OATP, OATP-B1, which could reduce the bioavailability and clinical effects of OATP-B1 substrates.
In vitro research shows that milk thistle inhibits OATP-B1. Two case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking milk thistle and cancer medications that are OATP substrates, including sorafenib and methotrexate. OATPs are expressed in the small intestine and liver and are responsible for the uptake of drugs and other compounds into the body. Inhibition of OATP may reduce the bioavailability of oral drugs that are substrates of OATP.
P-Glycoprotein Substrates
Theoretically, milk thistle might increase the absorption of P-glycoprotein substrates. However, this effect does not seem to be clinically significant.
In vitro research shows that milk thistle can inhibit P-glycoprotein activity and 1 case report from the World Health Organization (WHO) adverse drug reaction database describes increased abdominal pain in a patient taking milk thistle and the cancer medication vincristine, a P-glycoprotein substrate, though this patient was also taking methotrexate. However, a small pharmacokinetic study in healthy volunteers shows that taking milk thistle (Enzymatic Therapy Inc.) 900 mg, standardized to 80% silymarin, in 3 divided doses daily for 14 days does not affect absorption of digoxin, a P-glycoprotein substrate.
Niacin
Alcohol (Ethanol)
Concomitant use of alcohol and niacin might increase the risk of flushing and hepatotoxicity.
Alcohol can exacerbate the flushing and pruritus associated with niacin. Large doses of niacin might also exacerbate liver dysfunction associated with chronic alcohol use. A case report describes delirium and lactic acidosis in a patient taking niacin 3 grams daily who ingested 1 liter of wine. Advise patients to avoid large amounts of alcohol while taking niacin.
Allopurinol (Zyloprim)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as allopurinol.
Large doses of niacin can reduce urinary excretion of uric acid, potentially resulting in hyperuricemia. Doses of uricosurics such as allopurinol might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Anticoagulant/Antiplatelet Drugs
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Several cases of clotting factor synthesis deficiency and coagulopathy have been reported in patients taking sustained-release niacin. Also, thrombocytopenia has been reported in patients treated with niacin or niacin plus lovastatin.
Antidiabetes Drugs
Niacin can increase blood glucose levels and may diminish the effects of antidiabetes drugs.
Niacin impairs glucose tolerance in a dose-dependent manner, probably by causing or aggravating insulin resistance and increasing hepatic production of glucose. In diabetes patients, niacin 4.5 grams daily for 5 weeks can increase plasma glucose by an average of 16% and glycated hemoglobin (HbA1c) by 21%. However, lower doses of 1.5 grams daily or less appear to have minimal effects on blood glucose. In some patients, glucose levels increase when niacin is started, but then return to baseline when a stable dose is reached. Up to 35% of patients with diabetes may need adjustments in hypoglycemic therapy when niacin is added.
Antihypertensive Drugs
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
The vasodilating effects of niacin can cause hypotension. Furthermore, some clinical evidence suggests that a one-hour infusion of niacin can reduce systolic, diastolic, and mean blood pressure in hypertensive patients. This effect is not observed in normotensive patients.
Bile Acid Sequestrants
Bile acid sequestrants can bind niacin and decrease absorption. Separate administration by 4-6 hours to avoid an interaction.
In vitro studies show that colestipol (Colestid) binds about 98% of available niacin and cholestyramine (Questran) binds 10% to 30%.
Gemfibrozil (Lopid)
Theoretically, concomitant use of niacin and gemfibrozil might increase the risk of myopathy in some patients.
A case of myopathy from concomitant use of niacin and gemfibrozil has been reported. Niacin alone has also been associated with cases of myopathy. Using gemfibrozil with niacin might further increase the risk of developing myopathy.
Hepatotoxic Drugs
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Niacin has been associated with cases of liver toxicity, especially when used in pharmacologic doses. Sustained-release niacin preparations appear to be associated with a higher risk of hepatotoxicity than immediate-release niacin.
Hmg-Coa Reductase Inhibitors ("Statins")
Theoretically, concomitant use of niacin and statins might increase the risk of myopathy and rhabdomyolysis in some patients.
Some case reports have raised concerns that niacin might increase the risk of myopathy and rhabdomyolysis when combined with statins. However, a significantly increased risk of myopathy has not been demonstrated in clinical trials, including those using an FDA-approved combination of lovastatin and niacin (Advicor).
Probenecid (Benemid)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as probenecid.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as probenecid might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Sulfinpyrazone (Anturane)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as sulfinpyrazone.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as sulfinpyrazone might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Thyroid Hormone
Theoretically, niacin might antagonize the therapeutic effects of thyroid hormones.
Clinical research and case reports suggests that taking niacin can reduce serum levels of thyroxine-binding globulin by up to 25% and moderately reduce levels of thyroxine (T4). Patients taking thyroid hormone for hypothyroidism might need dose adjustments when using niacin.
Transdermal Nicotine (Nicoderm)
Theoretically, concomitant use of niacin and transdermal nicotine might increase the risk of flushing and dizziness.
Niacin and nicotine can both cause flushing and dizziness.
Warfarin (Coumadin)
There is limited evidence that niacin may increase the anticoagulant effects of warfarin.
In a case report, a patient on warfarin developed an elevated international normalized ratio (INR) of 3.9 after taking niacin for two weeks. The patient's INR was previously stable, ranging between 2 and 3 in recent months, and no other medication changes were identified. The elevated INR returned to therapeutic range within 4 days following the discontinuation of niacin.
Aspirin
Large doses of aspirin might alter the clearance of niacin.
Aspirin is often used with niacin to reduce niacin-induced flushing. Doses of 80-975 mg aspirin have been used, but 325 mg appears to be optimal. Aspirin also seems to reduce the clearance of niacin by competing for glycine conjugation. Taking aspirin 1 gram seems to reduce niacin clearance by 45%. This is probably a dose-related effect and not clinically significant with the more common aspirin dose of 325 mg.
Chelidonium majus
Cytochrome P450 2D6 (Cyp2D6) Substrates
Research in vitro shows that chelidonine, a constituent of greater celandine, inhibits cytochrome P450 2D6 (CYP2D6) enzyme activity. Theoretically, greater celandine might increase levels of drugs metabolized by CYP2D6.
Some drugs metabolized by CYP2D6 include amitriptyline (Elavil), clozapine (Clozaril), codeine, desipramine (Norpramin), donepezil (Aricept), fentanyl (Duragesic), flecainide (Tambocor), fluoxetine (Prozac), meperidine (Demerol), methadone (Dolophine), metoprolol (Lopressor, Toprol XL), olanzapine (Zyprexa), ondansetron (Zofran), tramadol (Ultram), trazodone (Desyrel), and many others.
Hepatotoxic Drugs
There is some concern that greater celandine can adversely affect the liver. Greater celandine has been linked to many cases of hepatotoxicity. Theoretically, concomitant use with other potentially hepatotoxic drugs might increase the risk of developing liver damage. Some of these drugs include acarbose (Precose, Prandase), amiodarone (Cordarone), atorvastatin (Lipitor), azathioprine (Imuran), carbamazepine (Tegretol), cerivastatin (Baycol), diclofenac (Voltaren), felbamate (Felbatol), fenofibrate (TriCor), fluvastatin (Lescol), gemfibrozil (Lopid), isoniazid, itraconazole, (Sporanox), ketoconazole (Nizoral), leflunomide (Arava), lovastatin (Mevacor), methotrexate (Rheumatrex), nevirapine (Viramune), niacin, nitrofurantoin (Macrodantin), pioglitazone (Actos), pravastatin (Pravachol), pyrazinamide, rifampin (Rifadin), ritonavir (Norvir), rosiglitazone (Avandia), simvastatin (Zocor), tacrine (Cognex), tamoxifen, terbinafine (Lamisil), valproic acid, and zileuton (Zyflo).
Immunosuppressants
Preliminary clinical research suggests that taking a specific semi-synthetic derivative of the greater celandine constituent chelidonine (Ukrain; not available in North America) might stimulate immune responses in cancer patients. Theoretically, taking greater celandine might decrease the effects of immunosuppressive therapy. Immunosuppressant drugs include azathioprine (Imuran), basiliximab (Simulect), cyclosporine (Neoral, Sandimmune), daclizumab (Zenapax), muromonab-CD3 (OKT3, Orthoclone OKT3), mycophenolate (CellCept), tacrolimus (FK506, Prograf), sirolimus (Rapamune), prednisone (Deltasone, Orasone), and other corticosteroids (glucocorticoids).
Monoamine Oxidase Inhibitors (Maois)
Theoretically taking monoamine oxidase inhibitors (MAOIs) with greater celandine might increase the risk of serotonergic side effects including serotonin syndrome. In vitro research shows that chelerythrine, an isoquinoline alkaloid in greater celandine, strongly, selectively, and reversibly inhibits an isoform of recombinant human monoamine oxidase-A (MAO-A). It was also a weak but selective inhibitor of monoamine oxidase-B (MAO-B). Some MAOIs include phenelzine (Nardil), tranylcypromine (Parnate), and others.
Dandelion
Anticoagulant/Antiplatelet Drugs
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
In vitro research suggests that dandelion root inhibits platelet aggregation.
Antidiabetes Drugs
Theoretically, dandelion might increase the risk for hypoglycemia when used with antidiabetes drugs.
Laboratory research suggests that dandelion extract may have moderate alpha-glucosidase inhibitor activity and might also increase insulin secretion. Also, in a case report, a 58-year-old woman with type 2 diabetes who was being treated with insulin developed hypoglycemia 2 weeks after beginning to eat salads containing dandelion.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Laboratory research suggests that dandelion might inhibit CYP1A2. So far, this interaction has not been reported in humans. However, until more is known, watch for an increase in the levels of drugs metabolized by CYP1A2 in patients taking dandelion.
Glucuronidated Drugs
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
There is some preliminary evidence that dandelion might induce UDP-glucuronosyltransferase, a phase II enzyme.
Lithium
Theoretically, through diuretic effects, dandelion might reduce excretion and increase levels of lithium.
Animal research suggests that dandelion has diuretic properties. As diuretics can increase serum lithium levels, the dose of lithium might need to be decreased when taken with dandelion.
Potassium-Sparing Diuretics
Theoretically, dandelion might increase the risk of hyperkalemia when taken with potassium-sparing diuretics.
Dandelion contains significant amounts of potassium.
Quinolone Antibiotics
Theoretically, dandelion might lower fluoroquinolone levels.
Animal research shows that dandelion reduces absorption of ciprofloxacin and can lower levels by 73%. However, this effect has not been reported in humans.
Club Moss
Acetylcholinesterase (Ache) Inhibitors
Evidence from in vitro research suggests that clubmoss extract can inhibit acetylcholinesterase activity. Theoretically, concurrent use of clubmoss with other acetylcholinesterase (AChE) inhibitors might have additive effects and increase the risk of cholinergic side effects. AChE inhibitors and cholinergic drugs include bethanechol (Urecholine), donepezil (Aricept), echothiophate (Phospholine Iodide), edrophonium (Enlon, Reversol, Tensilon), neostigmine (Prostigmin), physostigmine (Antilirium), pyridostigmine (Mestinon, Regonol), succinylcholine (Anectine, Quelicin), and tacrine (Cognex).
Anticholinergic Drugs
Evidence from in vitro research suggests that clubmoss extract can inhibit acetylcholinesterase activity. Theoretically, concurrent use of anticholinergic drugs and clubmoss might decrease the effectiveness of club moss or the anticholinergic agent. Some anticholinergic drugs include atropine, benztropine (Cogentin), biperiden (Akineton), procyclidine (Kemadrin), and trihexyphenidyl (Artane).
Cholinergic Drugs
Evidence from in vitro research suggests that clubmoss extract can inhibit acetylcholinesterase activity. Theoretically, concurrent use of clubmoss with other cholinergic drugs might have additive effects and increase the risk of cholinergic side effects. AChE inhibitors and cholinergic drugs include bethanechol (Urecholine), donepezil (Aricept), echothiophate (Phospholine Iodide), edrophonium (Enlon, Reversol, Tensilon), neostigmine (Prostigmin), physostigmine (Antilirium), pyridostigmine (Mestinon, Regonol), succinylcholine (Anectine, Quelicin), and tacrine (Cognex).
Pyridoxine
Amiodarone (Cordarone)
Theoretically, vitamin B6 might increase the photosensitivity caused by amiodarone.
Despite initial case reports suggesting that pyridoxine may have a protective effect against amiodarone-induced photosensitivity, preliminary clinical research suggests that pyridoxine may actually exacerbate this adverse effect.
Antihypertensive Drugs
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Research in hypertensive rats shows that vitamin B6 can decrease systolic blood pressure. Similarly, clinical research in patients with hypertension shows that taking high doses of vitamin B6 may reduce systolic and diastolic blood pressure, possibly by reducing plasma levels of epinephrine and norepinephrine.
Phenobarbital (Luminal)
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenobarbital, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenobarbital to avoid high doses of vitamin B6.
Phenytoin (Dilantin)
High doses of vitamin B6 may reduce the levels and clinical effects of phenytoin.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenytoin, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenytoin to avoid high doses of vitamin B6.
Levodopa
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Vitamin B6 (pyridoxine) enhances the metabolism of levodopa, reducing its clinical effects. However, this interaction does not occur when carbidopa is used concurrently with levodopa (Sinemet). Therefore, it is not likely to be a problem in most people.
Sodium Pyruvate
Antihypertensive Drugs
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
High intake of dietary sodium can increase systolic and diastolic blood pressure. Also, high intake of sodium may necessitate increased use of antihypertensive medications to achieve blood pressure control in some patients, such as those with chronic kidney disease.
Corticosteroids
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Mineralocorticoids and some glucocorticoids (corticosteroids) cause sodium retention. This effect is dose-related and depends on mineralocorticoid potency. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Didanosine (Videx)
Concomitant use of didanosine with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia.
Didanosine formulations contain a significant amount of sodium.
Lithium
Altering dietary intake of sodium might alter the levels and clinical effects of lithium.
High sodium intake can reduce plasma concentrations of lithium by increasing lithium excretion. Reducing sodium intake can significantly increase plasma concentrations of lithium and cause lithium toxicity in patients being treated with lithium carbonate. Stabilizing sodium intake is shown to reduce the percentage of patients with lithium level fluctuations above 0.8 mEq/L. Patients taking lithium should avoid significant alterations in their dietary intake of sodium.
Sodium Phosphates
Theoretically, concomitant use of sodium phosphate with sodium supplements might increase the risk of hypernatremia.
Use of high doses (> 45 mL in 24 hours) of sodium phosphate, such as those used for bowel cleansing before surgery, can lead to serious electrolyte disturbances, including hypernatremia. The risk of hypernatremia is highest in the elderly and people with other risk factors for electrolyte disturbances.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related complications.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium supplements or high-sodium diets, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Tolvaptan (Samsca)
Theoretically, concomitant use of tolvaptan with sodium might increase the risk of hypernatremia.
Tolvaptan is a vasopressin receptor 2 antagonist that is used to increase sodium levels in patients with hyponatremia. Patients taking tolvaptan should use caution with the use of sodium salts such as sodium chloride.
Inositol
Antidiabetes Drugs
Theoretically, taking inositol with antidiabetes drugs might increase the risk of hypoglycemia.
Clinical research shows that inositol lowers blood glucose levels and glycated hemoglobin (HbA1c) levels in patients with diabetes.
Potassium Sulfate
Ace Inhibitors (Aceis)
Using ACEIs with high doses of potassium increases the risk of hyperkalemia.
ACEIs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Angiotensin Receptor Blockers (Arbs)
Using ARBs with high doses of potassium increases the risk of hyperkalemia.
ARBs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Potassium-Sparing Diuretics
Concomitant use increases the risk of hyperkalemia.
Using potassium-sparing diuretics with potassium supplements increases the risk of hyperkalemia.
Blessed Thistle
Antacids
Theoretically, blessed thistle might decrease the effectiveness of antacids.
There are reports that blessed thistle increases stomach acid.
H2-Blockers
Theoretically, blessed thistle might decrease the effectiveness of H2-blockers.
There are reports that blessed thistle increases stomach acid.
Proton Pump Inhibitors (Ppis)
Theoretically, blessed thistle might decrease the effectiveness of PPIs.
There are reports that blessed thistle increases stomach acid.
Riboflavin
Tetracycline Antibiotics
Theoretically, taking riboflavin with tetracycline antibiotics may decrease the potency of these antibiotics.
In vitro research suggests that riboflavin may inhibit the potency of tetracycline antibiotics. It is not clear if this effect is clinically significant, as this interaction has not been reported in humans.
Vitamin B12
Metformin (Glucophage)
Metformin, a common medication used to manage type 2 diabetes, has been associated with lower vitamin B12 levels in some individuals. Prolonged use of metformin can interfere with the absorption of B12 in the digestive system, potentially leading to a deficiency in this essential vitamin.
Choline Chloride
Atropine
Theoretically, choline might decrease the effects of atropine in the brain.
Animal research shows that administering choline one hour before administering atropine can attenuate atropine-induced decreases in brain levels of acetylcholine. Theoretically, concomitant use of choline and atropine may decrease the effects of atropine.
Thiamine
Trimethoprim (Proloprim)
Trimethoprim might increase blood levels of thiamine.
In vitro, animal, and clinical research suggest that trimethoprim inhibits intestinal thiamine transporter ThTR-2, hepatic transporter OCT1, and renal transporters OCT2, MATE1, and MATE2, resulting in paradoxically increased thiamine plasma concentrations.
Brand information
Manufacturer and brand details for LiveXX, from the product label.
Viatrexx Bio Incorporated
See all Viatrexx Bio Incorporated products- Name
- Viatrexx
- Phone Number
- 1.888.743.6652
- Web Address
- Viatrexx.com
LiveXX by Viatrexx Bio Incorporated: Common Questions
Does LiveXX by Viatrexx Bio Incorporated interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Is LiveXX safe to take if I'm pregnant or breastfeeding?
Can I take LiveXX with my blood pressure or diabetes medication?
What do the B vitamins in LiveXX actually do?
What's the proprietary blend in LiveXX, and why isn't it listed in detail?
Can LiveXX cause side effects?
Is LiveXX vegan or free of animal products?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if LiveXX is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind LiveXX’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Thiamine
Interacts with 3 drugsThiamine (vitamin B1) is an essential nutrient your body needs to turn food into energy and to keep your nerves and heart healthy. Most people get enough from food, but supplements are clear...
Read the full Thiamine monograph → Herb & supplement monographVitamin B6
Interacts with 210 drugsVitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is best known for helping with pregnancy-rel...
Read the full Vitamin B6 monograph → Herb & supplement monographInositol
Interacts with 86 drugsInositol is a sugar alcohol made naturally in the body and found in many foods, and it is sold as a supplement (often myo-inositol) mainly for PCOS, mood, and metabolic concerns. The stronge...
Read the full Inositol monograph → Herb & supplement monographDandelion
Interacts with 457 drugsDandelion is a common plant used in food and traditional medicine, often promoted as a natural 'water pill' and digestive aid. Human evidence for these uses is very limited, so its benefits...
Read the full Dandelion monograph → Herb & supplement monographRiboflavin
Interacts with 20 drugsRiboflavin (vitamin B2) is an essential nutrient your body needs to turn food into energy and to keep skin, eyes, and nerves healthy. It is generally very safe at typical doses, and the stro...
Read the full Riboflavin monograph → Herb & supplement monographVitamin B12
Interacts with 20 drugsVitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very helpful for people who are deficient — su...
Read the full Vitamin B12 monograph → Herb & supplement monographMilk Thistle
Interacts with 954 drugsMilk thistle is a popular herbal supplement most often used for liver health, and its main active component is a group of compounds called silymarin. While it is generally well tolerated, th...
Read the full Milk Thistle monograph → Herb & supplement monographCholine
Interacts with 16 drugsCholine is an essential nutrient your body needs for liver function, brain health, and nerve signaling, and many people get enough from foods like eggs, meat, and fish. Supplements may help...
Read the full Choline monograph → Herb & supplement monographPotassium
Interacts with 62 drugsPotassium is an essential mineral your body needs for nerve signals, muscle function, and a steady heartbeat, and most people get enough from a balanced diet rich in fruits and vegetables. P...
Read the full Potassium monograph → Herb & supplement monographFringetree
Fringetree is a North American shrub whose root and stem bark have long been used in traditional herbal medicine, mainly for liver, gallbladder, and digestive complaints. There is very littl...
Read the full Fringetree monograph → Herb & supplement monographNiacin
Interacts with 727 drugsNiacin (vitamin B3) is an essential nutrient your body needs for energy and metabolism, and deficiency is uncommon in most developed countries. Prescription-strength niacin has been used to...
Read the full Niacin monograph → Herb & supplement monographBlessed Thistle
Interacts with 36 drugsBlessed thistle is a bitter herb traditionally used to stimulate appetite and ease mild digestive complaints. High-quality human studies are lacking, so its benefits are not well proven. It...
Read the full Blessed Thistle monograph → Herb & supplement monographNew Jersey Tea
New Jersey Tea is a North American shrub whose leaves were historically brewed as a caffeine-free tea and used in folk medicine for sore throats and other complaints. There is very little mo...
Read the full New Jersey Tea monograph → Herb & supplement monographGreater Celandine
Interacts with 625 drugsGreater celandine is a traditional herb most often promoted for digestive and gallbladder complaints, but solid human evidence for any use is lacking. More importantly, it has been linked to...
Read the full Greater Celandine monograph → Herb & supplement monographClubmoss
Interacts with 219 drugsClubmoss (Lycopodium clavatum) is a primitive plant with a long history in folk medicine and homeopathy, but there is very little reliable human research to show it works for any health cond...
Read the full Clubmoss monograph → Herb & supplement monographSodium
Interacts with 205 drugsSodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets get more than enough—often too much—from...
Read the full Sodium monograph →Sources & How We Checked
LiveXX's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 347 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Thiamine 7 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Rogovik, A. L., Vohra, S., and Goldman, R. D. Safety considerations and potential interactions of vitamins: should vitamins be considered drugs? Ann.Pharmacother. 2010;44(2):311-324. PubMed
- Arruti N, Bernedo N, Audicana MT, Villarreal O, Uriel O, Muñoz D. Systemic allergic dermatitis caused by thiamine after iontophoresis. Contact Dermatitis. 2013 Dec;69(6):375-6. PubMed
- Thiamine hydrochloride injection package insert. Lake Zurich, IL: Fresenius Kabi, LLC; September 2019.
- Vora B, Wen A, Yee SW, et al. The Effect of Trimethoprim on Thiamine Absorption: A Transporter-Mediated Drug-Nutrient Interaction. Clin Pharmacol Ther 2023;114(2):381-392.
Vitamin B6 32 references
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Geerling BJ, Dagnelie PC, Badart-Smook A, et al. Diet as a risk factor for the development of ulcerative colitis. Am J Gastroenterol 2000;95:1008-13. PubMed
- South M. Neonatal seizures after pyridoxine use -- reply. Lancet 1999;354:2083. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Baxter P, Aicardi J. Neonatal seizures after pyridoxine use. Lancet 1999;354:2082-3. PubMed
- Bendich A, Cohen M. Vitamin B6 safety issues. Ann N Y Acad Sci 1990;585:321-30.
- Schaumburg H, Kaplan J, Windebank A. Sensory neuropathy from pyridoxine abuse. A new megavitamin syndrome. N Engl J Med 1983;309:445-8. PubMed
- Gordon N. Pyridoxine dependency: an update. Dev Med Child Neurol 1997;39:63-5. PubMed
- Lewis PJ. Pain in the hand and wrist. Pyridoxine supplements may help patients with carpal tunnel syndrome. BMJ 1995;310:1534. PubMed
- Kaufman G. Pyridoxine against amiodarone-induced photosensitivity (letter). Lancet 1984;1:51-2. PubMed
- Mulrow JP, Mulrow CD, McKenna WJ. Pyridoxine and amiodarone-induced photosensitivity. Ann Intern Med 1985;103:68-9. PubMed
- Kawada A, Kashima A, Shiraishi H, et al. Pyridoxine-induced photosensitivity and hypophosphatasia. Dermatology 2000;201:356-60.. PubMed
- Vasile A, Goldberg R, Kornberg B. Pyridoxine toxicity: report of a case. J Am Osteopath Assoc 1984;83:790-1. DOI
- Hansson O, Sillanpaa M. Pyridoxine and serum concentration of phenytoin and phenobarbitone. Lancet 1976;1:256. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Chittumma P, Kaewkiattikun K, Wiriyasiriwach B. Comparison of the effectiveness of ginger and vitamin B6 for treatment of nausea and vomiting in early pregnancy: a randomized double-blind controlled trial. J Med Assoc Thai 2007;90:15-20.
- Hatzitolios, A., Iliadis, F., Katsiki, N., and Baltatzi, M. Is the anti-hypertensive effect of dietary supplements via aldehydes reduction evidence based? A systematic review. Clin Exp.Hypertens. 2008;30(7):628-639. PubMed
- Vasdev, S., Ford, C. A., Parai, S., Longerich, L., and Gadag, V. Dietary vitamin B6 supplementation attenuates hypertension in spontaneously hypertensive rats. Mol.Cell Biochem. 1999;200(1-2):155-162.
- de, Vogel S., Dindore, V., van, Engeland M., Goldbohm, R. A., van den Brandt, P. A., and Weijenberg, M. P. Dietary folate, methionine, riboflavin, and vitamin B-6 and risk of sporadic colorectal cancer. J Nutr 2008;138(12):2372-2378. PubMed
- Hagen, I., Nesheim, B. I., and Tuntland, T. No effect of vitamin B-6 against premenstrual tension. A controlled clinical study. Acta Obstet.Gynecol.Scand. 1985;64(8):667-670. PubMed
- Aybak, M., Sermet, A., Ayyildiz, M. O., and Karakilcik, A. Z. Effect of oral pyridoxine hydrochloride supplementation on arterial blood pressure in patients with essential hypertension. Arzneimittelforschung. 1995;45(12):1271-1273.
- Lal, K. J., Dakshinamurti, K., and Thliveris, J. The effect of vitamin B6 on the systolic blood pressure of rats in various animal models of hypertension. J Hypertens. 1996;14(3):355-363. PubMed
- Lauritzen CH, Reuter HD, Repges R, Bohnert K, and Schmidt U. Treatment of premenstrual tension syndrome with Vitex agnus castus. Controlled, double-blind study versus pyridoxine. Phytomed 1997;4(3):183-189. PubMed
- Fonseca VA, Lavery LA, Thethi TK, et al. Metanx in type 2 diabetes with peripheral neuropathy: A randomized trial. Am J Med 2013;126(2):141-9. PubMed
- Hankey GJ, Eikelboom JW, Yi Q, et al. Treatment with B vitamins and incidence of cancer in patients with previous stroke or transient ischemic attack: Results of a randomized placebo-controlled trial. Stroke 2012;43(6):1572-7. PubMed
- Hoyer-Kuhn H, Kohbrok S, Volland R, Franklin J, Hero B, Beck BB, Hoppe B. Vitamin B6 in primary hyperoxaluria I: first prospective trial after 40 years of practice. Clin J Am Soc Nephrol. 2014 Mar;9(3):468-77. PubMed
- Mahmoud A, Tabassum S, Al Enazi S, et al. Amelioration of levetiracetam-induced behavioral side effects by pyridoxine. A randomized double blind controlled study. Pediatr Neurol 2021;119:15-21. PubMed
- Gupta M, Gallante B, Bamberger JN, et al. Prospective randomized evaluation of idiopathic hyperoxaluria treatments. J Endourol 2021;35(12):1844-1851. PubMed
- Li H, Chen M, Liang S, et al. Excessive vitamin B6 during treatment is related to poor prognosis of patients with nasopharyngeal carcinoma: A U-shaped distribution suggests low dose supplement. Clin Nutr 2021;40(4):2293-2300. PubMed
- Tanigawa J, Nabatame S, Tominaga K, et al. High-dose pyridoxine treatment for inherited glycosylphosphatidylinositol deficiency. Brain Dev 2021;43(6):680-687. PubMed
- Committee on Practice Bulletins-Obstetrics. ACOG Practice Bulletin No. 189: Nausea And Vomiting Of Pregnancy. Obstet Gynecol. 2018;131(1):e15-e30. PubMed
Inositol 14 references
- Palatnik A, Frolov K, Fux M, Benjamin J. Double-blind, controlled, crossover trial of inositol versus fluvoxamine for the treatment of panic disorder. J Clin Psychopharmacol 2001;21:335-9.. PubMed
- Allan SJ, Kavanagh GM, Herd RM, Savin JA. The effect of inositol supplements on the psoriasis of patients taking lithium: a randomized, placebo-controlled trial. Br J Dermatol 2004;150:966-9. PubMed
- Machado-Vieira R, Viale CI, Kapczinski F. Mania associated with an energy drink: the possible role of caffeine, taurine, and inositol. Can J Psychiatry 2001;46:454-5. PubMed
- Kamenov Z, Kolarov G, Gateva A, Carlomagno G, Genazzani AD. Ovulation induction with myo-inositol alone and in combination with clomiphene citrate in polycystic ovarian syndrome patients with insulin resistance. Gynecol Endocrinol 2015;31(2):131-5. PubMed
- Matarrelli B, Vitacolonna E, D'Angelo M, et al. Effect of dietary myo-inositol supplementation in pregnancy on the incidence of maternal gestational diabetes mellitus and fetal outcomes: a randomized controlled trial. J Matern Fetal Neonatal Med 2013;26(1 PubMed
- Mukai T, Kishi T, Matsuda Y, Iwata N. A meta-analysis of inositol for depression and anxiety disorders. Hum Psychopharmacol 2014;29(1):55-63. PubMed
- Farren M, Daly N, McKeating A, Kinsley B, Turner MJ, Daly S. The Prevention of Gestational Diabetes Mellitus With Antenatal Oral Inositol Supplementation: A Randomized Controlled Trial. Diabetes Care. 2017;40(6):759-63. PubMed
- Zheng X, Liu Z, Zhang Y, et al. Relationship Between Myo-Inositol Supplementary and Gestational Diabetes Mellitus: A Meta-Analysis. Medicine (Baltimore). 2015;94(42):e1604. PubMed
- Crawford TJ, Crowther CA, Alsweiler J, Brown J. Antenatal dietary supplementation with myo-inositol in women during pregnancy for preventing gestational diabetes. Cochrane Database Syst Rev. 2015;(12):CD011507. PubMed
- Maurizi AR, Menduni M, Del Toro R, et al. A pilot study of D-chiro-inositol plus folic acid in overweight patients with type 1 diabetes. Acta Diabetol. 2017;54(4):361-65. PubMed
- Leppink EW, Redden SA, Grant JE. A double-blind, placebo-controlled study of inositol in trichotillomania. Int Clin Psychopharmacol. 2017;32(2):107-14. PubMed
- Lam S, Mandrekar SJ, Gesthalter Y. A Randomized Phase IIb Trial of myo-Inositol in Smokers with Bronchial Dysplasia. Cancer Prev Res (Phila). 2016;9(12):906-14.
- Wozniak J, Faraone SV, Chan J, et al. A randomized clinical trial of high eicosapentaenoic acid omega-3 fatty acids and inositol as monotherapy and in combination in the treatment of pediatric bipolar spectrum disorders: a pilot study. J Clin Psychiatry. PubMed
- Vitale SG, Corrado F, Caruso S, et al. Myo-inositol supplementation to prevent gestational diabetes in overweight non-obese women: bioelectrical impedance analysis, metabolic aspects, obstetric and neonatal outcomes - a randomized and open-label, placebo-
Dandelion 27 references
- Maliakal PP, Wanwimolruk S. Effect of herbal teas on hepatic drug metabolizing enzymes in rats. J Pharm Pharmacol 2001;53:1323-9. PubMed
- Williams CA, Goldstone F, Greenham J. Flavonoids, cinnamic acids and coumarins from the different tissues and medicinal preparations of Taraxacum officinale. Phytochemistry 1996;42:121-7. PubMed
- Hussain Z, Waheed A, Qureshi RA, et al. The effect of medicinal plants of Islamabad and Murree region of Pakistan on insulin secretion from INS-1 cells. Phytother Res 2004;18:73-7. PubMed
- Racz-Kotilla E, Racz G, Solomon A. The action of Taraxacum officinale extracts on the body weight and diuresis of laboratory animals. Planta Med 1974;26:212-7. PubMed
- Zhu M, Wong PY, Li RC. Effects of taraxacum mongolicum on the bioavailability and disposition of ciprofloxacin in rats. J Pharm Sci 1999;88:632-4. PubMed
- Jovanovic M, Mimica-Dukic N, Poljacki M, Boza P. Erythema multiforme due to contact with weeds: a recurrence after patch testing. Contact Dermatitis 2003;48:17-25. PubMed
- Chivato T, Juan F, Montoro A, Laguna R. Anaphylaxis induced by ingestion of a pollen compound. J Investig Allergol Clin Immunol 1996;6:208-9.
- Cohen SH, Yunginger JW, Rosenberg N, Fink JN. Acute allergic reaction after composite pollen ingestion. J Allergy Clin Immunol 1979;64:270-4. PubMed
- Lovell CR, Rowan M. Dandelion dermatitis. Contact Dermatitis 1991;25:185-8. PubMed
- Agarwal SC, Crook JR, Pepper CB. Herbal remedies -- how safe are they? A case report of polymorphic ventricular tachycardia/ventricular fibrillation induced by herbal medication used for obesity. Int J Cardiol 2006;106:260-1. PubMed
- Martín-Muñoz MF, Bartolome B, Caminoa M, et al. Bee pollen: a dangerous food for allergic children. Identification of responsible allergens. Allergol Immunopathol (Madr) 2010;38:263-5. PubMed
- Neef H, Cilli F, Declerck PJ, et al. Platelet anti-aggregating activity of Taraxacum officinale Weber. Phytotherapy Research 1996;10:s138-s140.
- Cuzzolin L, Zaffani S, and Benoni G. Safety implications regarding use of phytomedicines. Eur.J Clin Pharmacol. 2006;62:37-42. PubMed
- Posadzki, P., Watson, L. K., and Ernst, E. Adverse effects of herbal medicines: an overview of systematic reviews. Clin Med 2013;13(1):7-12. PubMed
- Wakelin, S. H., Marren, P., Young, E., and Shaw, S. Compositae sensitivity and chronic hand dermatitis in a seven-year-old boy. Br J Dermatol 1997;137(2):289-291. PubMed
- Ingber, A. Seasonal allergic contact dermatitis from Taraxacum officinale (dandelion) in an Israeli florist. Contact Dermatitis 2000;43(1):49.
- Rodriguez, B., Rodriguez, A., de Barrio, M., Tornero, P., and Baeza, M. L. Asthma induced by canary food mix. Allergy Asthma Proc. 2003;24(4):265-268.
- Syhaieva, I. A. [Efficiency of specific immunotherapy in treatment of patients with seasonal allergic rhinitis]. Lik.Sprava. 2006;(1-2):51-53.
- Catania, M. A., Oteri, A., Caiello, P., Russo, A., Salvo, F., Giustini, E. S., Caputi, A. P., and Polimeni, G. Hemorrhagic cystitis induced by an herbal mixture. South.Med.J. 2010;103(1):90-92. PubMed
- Goksu, E., Eken, C., Karadeniz, O., and Kucukyilmaz, O. First report of hypoglycemia secondary to dandelion (Taraxacum officinale) ingestion. Am J Emerg.Med 2010;28(1):111-112. PubMed
- Fernandez-Gonzalez, D., Gonzalez-Parrado, Z., Vega-Maray, A. M., Valencia-Barrera, R. M., Camazon-Izquierdo, B., De, Nuntiis P., and Mandrioli, P. Platanus pollen allergen, Pla a 1: quantification in the atmosphere and influence on a sensitizing populati
- Liang, K. L., Su, M. C., Shiao, J. Y., Wu, S. H., Li, Y. H., and Jiang, R. S. Role of pollen allergy in Taiwanese patients with allergic rhinitis. J Formos.Med Assoc. 2010;109(12):879-885. PubMed
- Yang, Y., Zhao, Y., Wang, C. S., Wang, X. D., and Zhang, L. [Prevalence of sensitization to aeroallergens in 10 030 patients with allergic rhinitis]. Zhonghua Er.Bi Yan.Hou Tou.Jing.Wai Ke Za Zhi 2011;46(11):914-920.
- Davies, M. G. and Kersey, P. J. Contact allergy to yarrow and dandelion. Contact Dermatitis 1986;14(4):256-257. PubMed
- Collins JM and Miller DR. Dandelion green bezoar following antrectomy and vagotomy - case report. J Kansas Med Soc 1966;67(6):303-304.
- Moriarty B, Pinney JH, Owen-Casey MP, Rustin MH, Deroide F, Laing C, Davenport A. Digital necrosis from dandelion tea. Br J Dermatol. 2013 Jul;169(1):227-30. PubMed
- Onal S, Timur S, Okutucu B, Zihnioglu F. Inhibition of alphaglucosidase by aqueous extracts of some potent antidiabetic medicinal herbs. Prep Biochem Biotechnol 2005;35:29-36.
Riboflavin 5 references
- Schoenen J, Jacquy J, Lenaerts M. Effectiveness of high-dose riboflavin in migraine prophylaxis. A randomized controlled trial. Neurology 1998;50:466-70. PubMed
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Leeson LJ, Weidenheimer JF. Stability of tetracycline and riboflavin. J Pharm Sci. 1969;58(3):355-7. PubMed
- MacLennan, S. C., Wade, F. M., Forrest, K. M., Ratanayake, P. D., Fagan, E., and Antony, J. High-dose riboflavin for migraine prophylaxis in children: a double-blind, randomized, placebo-controlled trial. J Child Neurol. 2008;23(11):1300-1304.
- Dietary reference intakes (DRIs): estimated average requirements. Food and Nutrition Board, Institute of Medicine, National Academics. https://www.nal.usda.gov/sites/default/files/fnic_uploads//recommended_intakes_individuals.pdf Accessed July 24, 2017.
Vitamin B12 30 references
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Hartman TJ, Woodson K, Stolzenberg-Solomon R, et al. Association of the B-vitamins pyridoxal 5'-phosphate (B6), B12, and folate with lung cancer risk in older men. Am J Epidemiol 2001;153:688-94.. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Lange H, Suryapranata H, De Luca G, et al. Folate therapy and in-stent restenosis after coronary stenting. N Engl J Med 2004;350:2673-81. PubMed
- Collin, S. M., Metcalfe, C., Refsum, H., Lewis, S. J., Zuccolo, L., Smith, G. D., Chen, L., Harris, R., Davis, M., Marsden, G., Johnston, C., Lane, J. A., Ebbing, M., Bonaa, K. H., Nygard, O., Ueland, P. M., Grau, M. V., Baron, J. A., Donovan, J. L., Nea
- Geissbuhler, P., Mermillod, B., and Rapin, C. H. Elevated serum vitamin B12 levels associated with CRP as a predictive factor of mortality in palliative care cancer patients: a prospective study over five years. J.Pain Symptom.Manage. 2000;20(2):93-103. PubMed
- Salles, N., Herrmann, F., Sakbani, K., Rapin, C. H., and Sieber, C. High vitamin B12 level: a strong predictor of mortality in elderly inpatients. J Am Geriatr.Soc 2005;53(5):917-918.
- Looker, H. C., Fagot-Campagna, A., Gunter, E. W., Pfeiffer, C. M., Sievers, M. L., Bennett, P. H., Nelson, R. G., Hanson, R. L., and Knowler, W. C. Homocysteine and vitamin B(12) concentrations and mortality rates in type 2 diabetes. Diabetes Metab Res R
- Uhl, W., Nolting, A., Golor, G., Rost, K. L., and Kovar, A. Safety of hydroxocobalamin in healthy volunteers in a randomized, placebo-controlled study. Clin Toxicol (Phila) 2006;44 Suppl 1:17-28. PubMed
- Borron, S. W., Baud, F. J., Barriot, P., Imbert, M., and Bismuth, C. Prospective study of hydroxocobalamin for acute cyanide poisoning in smoke inhalation. Ann Emerg.Med 2007;49(6):794-801, 801. PubMed
- Borron, S. W., Baud, F. J., Megarbane, B., and Bismuth, C. Hydroxocobalamin for severe acute cyanide poisoning by ingestion or inhalation. Am J Emerg.Med 2007;25(5):551-558. PubMed
- Lewis, J. G. Gout, Steatorrhoea, and Megaloblastic Anaemia. Ann Rheum.Dis 1962;21(3):284-286. PubMed
- Tal, S., Shavit, Y., Stern, F., and Malnick, S. Association between vitamin B12 levels and mortality in hospitalized older adults. J Am Geriatr.Soc 2010;58(3):523-526. PubMed
- Baztan, J. J., Gavidia, J. J., Gomez-Pavon, J., Esteve, A., and Ruiperez, I. High vitamin B12 levels and in-hospital mortality. J Am Geriatr.Soc 2010;58(11):2237-2238. PubMed
- Omboni, E., Checchini, M., and Longoni, F. [Hypopotassemia and megaloblastic anemia. Presentation of a case]. Minerva Med 8-31-1987;78(16):1255-1257.
- Aalfs As, Scholvinck LH, Horvath B. Acneiform eruption in a 5-year old due to vitamin B12 supplementation. Eur J Dermatol 2013;23(5):726-7. PubMed
- Balta I, Ozuguz P. Vitamin B12-induced acneiform eruption. Cutan Ocul Toxicol 2014;33(2):94-5. PubMed
- Carman KB, Belgemen T, Yis U. Involuntary movements misdiagnosed as seizure during vitamin B12 treatment. Pediatr Emerg Care 2013;29(11):1223-4. PubMed
- Djuric V, Bogic M, Popadic AP, et al. Anaphylactic reaction to hydroxycobalamin with tolerance to cyanocobalamin. Ann Allergy Asthma Immunol 2012;108(3):207-8. PubMed
- Kartel O, Gulec M, Demirel F, et al. Vitamin B12 allergy and successful desensitization with cyanocobalamin: A case report. Allergol Immunopath (Madr) 2012;40(5):324-5.
- Patiroglu T, Unal E, Yildirim S. Infantile tremor syndrome associated with cobalamin therapy: A case report. Clin Neurol Neurosurg 2013;115(9):1903-5. PubMed
- Schulte S, Barkema LW, Kardaun SH. Long-lasting atypical acneiform eruption with prominent comedones induced by hydroxocobalamin (vitamin B12). J Dtsch Dermatol Ges 2014;12(6):502-3.
- Zanus C, Alberini E, Costa P, et al. Involuntary movements after correction of vitamin B12 deficiency: A video-case report. Epileptic Disord 2012;14(2):174-80. PubMed
- Fanidi A, Carreras-Torres R, Larose TL, et al. Is high vitamin B12 status a cause of lung cancer? Int J Cancer. 2019 Sep 15;145(6):1499-1503. PubMed
- Fujita Y, Mizukami T, Maya Y, et al. Vitamin B12 allergy manifesting as lymphomatoid contact dermatitis. Eur J Dermatol. 2020;30(3):304-305. PubMed
- Dépret F, Hoffmann C, Daoud L, et al. Association between hydroxocobalamin administration and acute kidney injury after smoke inhalation: a multicenter retrospective study. Crit Care. 2019;23(1):421. PubMed
- Khairan P, Sobue T, Eshak ES, et al. Association of dietary intakes of vitamin B12, vitamin B6, folate, and methionine with the risk of esophageal cancer: the Japan Public Health Center-based (JPHC) prospective study. BMC Cancer 2021;21(1):982. PubMed
- Evans J, Pandya A, Ding Y, Qunibi WY. Hydroxocobalamin-Induced Oxalate Nephropathy in a Patient With Smoke Inhalation. Kidney Int Rep 2021;6(8):2228-2231. PubMed
- Lacombe V, Chabrun F, Lacout C, et al. Persistent elevation of plasma vitamin B12 is strongly associated with solid cancer. Sci Rep 2021;11(1):13361. PubMed
- Pegalajar-García MD, Cebolla-Verdugo M, Prados-Carmona Á, Llamas-Segura C, Navarro-Triviño FJ. Systemic allergic dermatitis to cobalt present in cyanocobalamin supplementation. Contact Dermatitis 2023;89(3):203-205. PubMed
Milk Thistle 69 references
- Ferenci P, Dragosics B, Dittrich H, et al. Randomized controlled trial of silymarin treatment in patients with cirrhosis of the liver. J Hepatol 1989;9:105-13. PubMed
- Anon. Milk thistle: Effects on liver disease and cirrhosis and clinical adverse effects. Summary, Evidence Report/Technology Assessment: Number 21, September 2000. Agency for Healthcare Research and Quality, Rockville, MD. Available at: http://www.ahrq.g
- Beckmann-Knopp S, Rietbrock S, Weyhenmeyer R, et al. Inhibitory effects of silibinin on cytochrome P-450 enzymes in human liver microsomes. Pharmacol Toxicol 2000;86:250-6. PubMed
- Venkataramanan R, Ramachandran V, Komoroski BJ, et al. Milk thistle, a herbal supplement, decreases the activity of CYP3A4 and uridine diphosphoglucuronosyl transferase in human hepatocyte cultures. Drug Metab Dispos 2000;28:1270-3. DOI
- Kim DH, Jin YH, Park JB, Kobashi K. Silymarin and its components are inhibitors of beta-glucuronidase. Biol Pharm Bull 1994;17:443-5. PubMed
- Pares A, Planas R, Torres M, et al. Effects of silymarin in alcoholic patients with cirrhosis of the liver: results of a controlled, double-blind, randomized and multicenter trial. J Hepatol 1998;28:615-21. PubMed
- Piscitelli SC, Formentini E, Burstein AH, et al. Effect of milk thistle on the pharmacokinetics of indinavir in healthy volunteers. Pharmacotherapy 2002;22:551-6. PubMed
- Boerth J, Strong KM. The clinical utility of milk thistle (Silybum marianum) in cirrhosis of the liver. J Herb Pharmacother 2002;2:11-7.
- Tanamly MD, Tadros F, Labeeb S, et al. Randomised double-blinded trial evaluating silymarin for chronic hepatitis C in an Egyptian village: study description and 12-month results. Dig Liver Dis 2004;36:752-9. PubMed
- Gurley BJ, Gardner SF, Hubbard MA, et al. In vivo assessment of botanical supplementation on human cytochrome P450 phenotypes: Citrus aurantium, Echinacea purpurea, milk thistle, and saw palmetto. Clin Pharmacol Ther 2004;76:428-40. .
- Huseini HF, Larijani B, Heshmat R, et al. The efficacy of Silybum marianum (L.) Gaertn. (silymarin) in the treatment of type II diabetes: a randomized, double-blind, placebo-controlled, clinical trial. Phytother Res 2006;20;1036-9.
- Deng JW, Shon JH, Shin HJ, et al. Effect of silymarin supplement on the pharmacokinetics of rosuvastatin. Pharm Res 2008;25:1807-14. PubMed
- Kim CS, Choi SJ, Park CY, et al. Effects of silybinin on the pharmacokinetics of tamoxifen and its active metabolite, 4-hydroxytamoxifen in rats. Anticancer Res 2010;30:79-85.
- Sridar C, Goosen TC, Kent UM, et al. Silybin inactivates cytochromes P450 3A4 and 2C9 and inhibits major hepatic glucuronosyltransferases. Drug Metab Dispos 2004;32:587-94. PubMed
- van Erp NP, Baker SD, Zhao M, et al. Effect of milk thistle (Silybum marianum) on the pharmacokinetics of irinotecan. Clin Cancer Res 2005;11:7800-6.
- Budzinski JW, Trudeau VL, Drouin CE, et al. Modulation of human cytochrome P450 3A4 (CYP3A4) and P-glycoprotein (P-gp) in Caco-2 cell monolayers by selected commercial-source milk thistle and goldenseal products. Can J Physiol Pharmacol 2007;85:966-78.
- Doehmer J, Weiss G, McGregor GP, Appel K. Assessment of a dry extract from milk thistle (Silybum marianum) for interference with human liver cytochrome-P450 activities. Toxicol In Vitro 2011;25:21-7. PubMed
- Jiao Z, Shi XJ, Li ZD, et al. Population pharmacokinetics of sirolimus in de novo Chinese adult renal transplant patients. Br.J.Clin.Pharmacol. 2009;68(1):47-60.
- Gurley, B. J., Barone, G. W., Williams, D. K., Carrier, J., Breen, P., Yates, C. R., Song, P. F., Hubbard, M. A., Tong, Y., and Cheboyina, S. Effect of milk thistle (Silybum marianum) and black cohosh (Cimicifuga racemosa) supplementation on digoxin phar
- Allain, H., Schuck, S., Lebreton, S., Strenge-Hesse, A., Braun, W., Gandon, J. M., and Brissot, P. Aminotransferase levels and silymarin in de novo tacrine-treated patients with Alzheimer's disease. Dement.Geriatr.Cogn Disord. 1999;10(3):181-185. PubMed
- Angulo, P., Patel, T., Jorgensen, R. A., Therneau, T. M., and Lindor, K. D. Silymarin in the treatment of patients with primary biliary cirrhosis with a suboptimal response to ursodeoxycholic acid. Hepatology 2000;32(5):897-900. PubMed
- Bean, P. The use of alternative medicine in the treatment of hepatitis C. Am.Clin.Lab 2002;21(4):19-21.
- Hussain, S. A. Silymarin as an adjunct to glibenclamide therapy improves long-term and postprandial glycemic control and body mass index in type 2 diabetes. J.Med.Food 2007;10(3):543-547. PubMed
- El-Kamary, S. S., Shardell, M. D., Abdel-Hamid, M., Ismail, S., El-Ateek, M., Metwally, M., Mikhail, N., Hashem, M., Mousa, A., Aboul-Fotouh, A., El-Kassas, M., Esmat, G., and Strickland, G. T. A randomized controlled trial to assess the safety and effic
- Gharagozloo, M., Moayedi, B., Zakerinia, M., Hamidi, M., Karimi, M., Maracy, M., and Amirghofran, Z. Combined therapy of silymarin and desferrioxamine in patients with beta-thalassemia major: a randomized double-blind clinical trial. Fundam.Clin.Pharmaco
- Ladas, E. J., Kroll, D. J., Oberlies, N. H., Cheng, B., Ndao, D. H., Rheingold, S. R., and Kelly, K. M. A randomized, controlled, double-blind, pilot study of milk thistle for the treatment of hepatotoxicity in childhood acute lymphoblastic leukemia (ALL PubMed
- Sayyah, M., Boostani, H., Pakseresht, S., and Malayeri, A. Comparison of Silybum marianum (L.) Gaertn. with fluoxetine in the treatment of Obsessive-Compulsive Disorder. Prog.Neuropsychopharmacol.Biol.Psychiatry 3-17-2010;34(2):362-365. PubMed
- Flaig, T. W., Glode, M., Gustafson, D., van, Bokhoven A., Tao, Y., Wilson, S., Su, L. J., Li, Y., Harrison, G., Agarwal, R., Crawford, E. D., Lucia, M. S., and Pollak, M. A study of high-dose oral silybin-phytosome followed by prostatectomy in patients w
- Ramirez-Santos, A., Perez-Bustillo, A., Gonzalez-Sixto, B., Suarez-Amor, O., and Rodriguez-Prieto, M. A. [Acute generalized exanthematous pustulosis due to milk thistle (Silybum marianum) tea]. Actas Dermosifiliogr. 2011;102(9):744-745. DOI
- Loguercio C, Andreone P, Brisc C, et al. Silybin combined with phosphatidylcholine and vitamin E in patients with nonalcoholic fatty liver disease: a randomized controlled trial. Free Radic Biol Med 2012;52(9):1658-65. PubMed
- Yakoot, M. and Salem, A. Spirulina platensis versus silymarin in the treatment of chronic hepatitis C virus infection. A pilot randomized, comparative clinical trial. BMC.Gastroenterol. 2012;12:32. PubMed
- Fallahzadeh, M. K., Dormanesh, B., Sagheb, M. M., Roozbeh, J., Vessal, G., Pakfetrat, M., Daneshbod, Y., Kamali-Sarvestani, E., and Lankarani, K. B. Effect of addition of silymarin to renin-angiotensin system inhibitors on proteinuria in type 2 diabetic
- Fried, M. W., Navarro, V. J., Afdhal, N., Belle, S. H., Wahed, A. S., Hawke, R. L., Doo, E., Meyers, C. M., and Reddy, K. R. Effect of silymarin (milk thistle) on liver disease in patients with chronic hepatitis C unsuccessfully treated with interferon t
- Fallah Huseini, H., Larijani, B., Fakhrzadeh, H., Rajabi Pour, B., Akhondzadeh, S., Toliat, T., and Heshmat, R. The clinical trial of Silybum Marianum seed extract (Silymarin) on type II diabetic patients with hyperlipidemia. Iran J.Diabetes Lipid Disord
- Mironets VI, Krasovskaia EA, and Polishchuk II. [A case of urticaria during Carsil treatment]. Vrach Delo 1990;7:86-87.
- Velussi M, Cernigoi AM, Viezzoli L, and et al. Silymarin reduces hyperinsulinemia, malondialdehyde levels, and daily insulin need in cirrhotic diabetic patients. Curr Ther Res 1993;53(5):533-545. DOI
- Marcelli R, Bizzoni P, Conte D, and et al. Randomized controlled study of the efficacy and tolerability of a short course of IdB 1016 in the treatment of chronic persistent hepatitis. Eur Bull Drug Res 1992;1(3):131-135.
- Vailati A, Aristia L, Sozze E, and et al. Randomized open study of the dose-effect relationship of a short course of IdB 1016 in patients with viral or alcoholic hepatitis. Fitoterapia 1993;64(3):219-228.
- Marena C and Lampertico M. Preliminary clinical development of silipide: a new complex of silybin in toxic liver disorders. Planta Med 1991;57(2):A124-A125. DOI
- Grungreiff K, Albrecht M, and Strenge-Hesse A. Benefit of medicinal liver therapy in general practice. Med Welt 1995;46:222-227.
- Frerick F, Kuhn U, and Strenge-Hesse A. Silymarin--ein Phytopharmakon zur Behandlung toxischen Leberschaden: Anwendungsbeobachtung bei 2169 Patienten. Kassenarzt 1990;33:36-41.
- Schuppan D, Strosser W, Burkard G, and et al. Influence of Legalon(TM) 140 on the metabolism of collagen in patients with chronic liver disease--Review by measurement of PIIINP-values. Zeitschrift fur Allgemeinmedizin 1998;74:577-584.
- Studlar M. Die Behandlung chronischer Leberkrankungen mit Silymarin und B-Vitaminen. Therapiewoche 1985;35:3375-3378.
- Anon. Adverse reaction: milk thistle-associated toxicity. Nurse Drug Alert 1999;23(7):51.
- Gufford BT, Chen G, Vergara AG, et al. Milk Thistle Constituents Inhibit Raloxifene Intestinal Glucuronidation: A Potential Clinically Relevant Natural Product-Drug Interaction. Drug Metab Dispos. 2015;43(9):1353-9. PubMed
- El-Shitany NA, Hegazy S, El-Desoky K. Evidences for antiosteoporotic and selective estrogen receptor modulator activity of silymarin compared with ethinylestradiol in ovariectomized rats. Phytomedicine. 2010;17(2):116-25. PubMed
- Seidlová-Wuttke D, Becker T, Christoffel V, Jarry H, Wuttke W. Silymarin is a selective estrogen receptor beta (ERbeta) agonist and has estrogenic effects in the metaphysis of the femur but no or antiestrogenic effects in the uterus of ovariectomized (ovx
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Derosa G, Romano D, D'Angelo A, Maffioli P. Berberis aristata/Silybum marianum fixed combination (Berberol(®)) effects on lipid profile in dyslipidemic patients intolerant to statins at high dosages: a randomized, placebo-controlled, clinical trial. Phyto PubMed
- Luangchosiri C, Thakkinstian A, Chitphuk S, Stitchantrakul W, Petraksa S, Sobhonslidsuk A. A double-blinded randomized controlled trial of silymarin for the prevention of antituberculosis drug-induced liver injury. BMC Complement Altern Med. 2015;15:334. PubMed
- Kawaguchi-Suzuki M, Frye RF, Zhu HJ, et al. The effects of milk thistle (Silybum marianum) on human cytochrome P450 activity. Drug Metab Dispos. 2014;42(10):1611-6. PubMed
- Rastegarpanah M, Malekzadeh R, Vahedi H, et al. A randomized, double blinded, placebo-controlled clinical trial of silymarin in ulcerative colitis. Chin J Integr Med. 2015;21(12):902-6. PubMed
- Di Pierro F, Bellone I, Rapacioli G, Putignano P. Clinical role of a fixed combination of standardized Berberis aristata and Silybum marianum extracts in diabetic and hypercholesterolemic patients intolerant to statins. Diabetes Metab Syndr Obes. 2015;8:8 PubMed
- Di Pierro F, Villanova N, Agostini F, Marzocchi R, Soverini V, Marchesini G. Pilot study on the additive effects of berberine and oral type 2 diabetes agents for patients with suboptimal glycemic control. Diabetes Metab Syndr Obes. 2012;5:213-7. PubMed
- Guarino G, Strollo F, Carbone L, et al. Bioimpedance analysis, metabolic effects and safety of the association Berberis aristata/Bilybum marianum: a 52-week double-blind, placebo-controlled study in obese patients with type 2 diabetes. J Biol Regul Homeos
- Ebrahimpour-Koujan S, Gargari BP, Mobasseri M, Valizadeh H, Asghari-Jafarabadi M. Lower glycemic indices and lipid profile among type 2 diabetes mellitus patients who received novel dose of Silybum marianum (L.) Gaertn. (silymarin) extract supplement: A T
- Lash DB, Ward S. CYP2C9-mediated warfarin and milk thistle interaction. J Clin Pharm Ther. 2019. PubMed
- Malekshah RE, Khaleghian A. Influence of Silybum marianum on morphine addicted rats, biochemical parameters and molecular simulation studies on µ-opioid receptor. Drug Res (Stuttg). 2019;69(11):630-638. PubMed
- Soleymani S, Ayati MH, Mansourzadeh MJ, Namazi N, Zargaran A. The effects of Silymarin on the features of cardiometabolic syndrome in adults: A systematic review and meta-analysis. Phytother Res. 2022 Jan 11. doi: 10.1002/ptr.7364. PubMed
- Gamissans M, Expósito-Serrano V, López-Llunell C, Valdivieso L, Garbayo-Salmons P. Bullous pemphigoid triggered by Silybum marianum: an unexpected side effect of an herbal remedy. Int J Dermatol. 2021 Aug 7. doi: 10.1111/ijd.15822. PubMed
- Aboras SI, Korany MA, El-Yazbi AF, Ragab MAA, Abdine HH. In-depth investigation of the Silymarin effect on the pharmacokinetic parameters of sofosbuvir, GS-331007 and ledipasvir in rat plasma using LC-MS. Biomed Chromatogr 2022;36(9):e5427. PubMed
- Wattanakrai P, Nimmannitya K. A Randomized, Double-Blind, Split-Face Study of Topical Silymarin vs 2% Hydroquinone Cream in Melasmas. J Drugs Dermatol 2022;21(12):1304-1310. PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
- Zhang W, Zhang Y, Wen C, Jiang X, Wang L. In vitro Assessment of the Effects of Silybin on CYP2B6-mediated Metabolism. Planta Med 2023. PubMed
- Bechtold BJ, Lynch KD, Oyanna VO, et al. Rifampin- and Silymarin-Mediated Pharmacokinetic Interactions of Exogenous and Endogenous Substrates in a Transgenic OATP1B Mouse Model. Mol Pharm 2024;21(5):2284-2297. PubMed
- Mohammadi S, Asbaghi O, Afrisham R, et al. Impacts of Supplementation with Silymarin on Cardiovascular Risk Factors: A Systematic Review and Dose-Response Meta-Analysis. Antioxidants (Basel) 2024;13(4):390. PubMed
- Rustamzadeh A, Sadigh N, Vahabi Z, et al. Effects silymarin and rosuvastatin on amyloid-carriers level in dyslipidemic Alzheimer's patients: A double-blind placebo-controlled randomized clinical trial. IBRO Neurosci Rep 2024;17:108-121. PubMed
- Fatemi Shandiz A, Karimi G, Dayyani M, Hosseini S, Elyasi S. Evaluation of oral silymarin formulation efficacy in prevention of doxorubicin induced hepatotoxicity in patients with non-metastatic breast cancer. J Oncol Pharm Pract 2024. PubMed
- Duan X, Bai W, Hu J, et al. Inhibitory effect of flavonoids on multidrug and toxin extrusion protein 1 function: Implications for food/herb-drug interaction and drug-induced kidney injury. J Appl Toxicol 2024;44(9):1388-1402. PubMed
Choline 14 references
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Cho E, Willett WC, Colditz GA, et al. Dietary choline and betaine and the risk of distal colorectal adenoma in women. J Natl Cancer Inst 2007;99:1224-31. PubMed
- Schmidt, C., Abicht, A., Krampfl, K., Voss, W., Stucka, R., Mildner, G., Petrova, S., Schara, U., Mortier, W., Bufler, J., Huebner, A., and Lochmuller, H. Congenital myasthenic syndrome due to a novel missense mutation in the gene encoding choline acetyl
- Tamminga, C., Smith, R. C., Chang, S., Haraszti, J. S., and Davis, J. M. Depression associated with oral choline. Lancet 10-23-1976;2(7991):905. PubMed
- Wood, J. L. and Allison, R. G. Effects of consumption of choline and lecithin on neurological and cardiovascular systems. Fed.Proc. 1982;41(14):3015-3021.
- Growdon, J. H. and Gelenberg, A. J. Choline and lecithin administration to patients with tardive dyskinesia. Trans.Am.Neurol.Assoc. 1978;103:95-99.
- Smith, C. M., Swash, M., Exton-Smith, A. N., Phillips, M. J., Overstall, P. W., Piper, M. E., and Bailey, M. R. Choline therapy in Alzheimer's disease. Lancet 8-5-1978;2(8084):318. PubMed
- Morrison, L. M. and W. F. Gonzales. Choline in coronary atherosclerosis. Amer.Heart J. 1950;39:729.
- Christie, J. G. Blackburn 1. M. Glen A. I. M. Zeisel S. Shering A. & Yates C. M. Effects of choline and lecithin on CSF choline levels and on cognitive functioning in patients with presenile dementia of the Alzheimer type. Nutrition and the brain 1979;5
- Sidhu N, Davies S, Nadarajah A, et al. Oral choline supplementation for postoperative pain. Br J Anaesth 2013;111(2):249-55. PubMed
- Wozniak JR, Fuglestad AJ, Eckerle JK, et al. Choline supplementation in children with fetal alcohol spectrum disorders has high feasibility and tolerability. Nutr Res. 2013;33(11):897-904. PubMed
- Wozniak JR, Fuglestad AJ, Eckerle JK, et al. Choline supplementation in children with fetal alcohol disorders: a randomized, double-blind, placebo-controlled trial. Am J Clin Nutr. 2015;102(5): 1113-25.
- Ross RG, Hunter SK, McCarthy L, et al. Perinatal choline effects on neonatal pathophysiology related to later schizophrenia risk. Am J Psychiatry. 2013;170(3):290-8. PubMed
- Food and Nutrition Board, Institute of Medicine. Choline. Dietary Reference Intakes: Thiamin, Riboflavin, Niacin, Vitamin B-6, Vitamin B-12, Pantothenic Acid, Biotin, and Choline. Washington D.C.: National Academy Press; 1998:390-422.
Potassium 12 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Gennaro A. Remington: The Science and Practice of Pharmacy. 19th ed. Lippincott: Williams & Wilkins, 1996.
- Whelton PK, He J, Cutler JA, et al. Effects of oral potassium on blood pressure. Meta-analysis of randomized controlled clinical trials. JAMA 1997;277:1624-32. PubMed
- Phillips, C. O., Kashani, A., Ko, D. K., Francis, G., and Krumholz, H. M. Adverse effects of combination angiotensin II receptor blockers plus angiotensin-converting enzyme inhibitors for left ventricular dysfunction: a quantitative review of data from ra DOI
- Altieri, P. I., Herrero, C., Suero, R., and Ortiz, A. Bleeding duodenal ulcer in a patient taking slow-releasing potassium tablets. Bol.Asoc.Med P.R. 1977;69(8):276.
- Raf, L. E. Enteric-coated potassium chloride tablets and ulcer of the small intestine. Acta Chir Scand Suppl 1967;(374):1-87.
- Potassium chloride oral solution [package insert]. Allentown, PA: Lehigh Valley Technologies, Inc.; 2014.
- Potassium chloride injection [package insert]. Lake Forest, IL: Hospira Inc.; 2009.
- Patel RB, Tannenbaum S, Viana-Tejedor A, et al. Serum potassium levels, cardiac arrhythmias, and mortality following non-ST-elevation myocardial infarction or unstable angina: insights from MERLIN-TIMI 36. Eur Heart J Acute Cardiovasc Care 2017 Feb;6(1):1 PubMed
- Malta D, Arcand J, Ravindran A, Floras V, Allard JP, Newton GE. Adequate intake of potassium does not cause hyperkalemia in hypertensive individuals taking medications that antagonize the renin angiotensin aldosterone system. Am J Clin Nutr 2016 Oct;104(4 PubMed
- Keskin M, Kaya A, Tatlisu MA, et al. The effect of serum potassium level on in-hospital and long-term mortality in ST elevation myocardial infarction. Int J cardiol. 2016 Oct 15;221:505-10.
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
Fringetree 2 references
Niacin 66 references
- Garg R, Malinow MR, Pettinger M, et al. Niacin treatment increases plasma homocysteine levels. Am Heart J 1999;138:1082-7.
- Anon. Inositol hexaniacinate. Altern Med Rev 1998;3:222-3.
- Knodel LC, Talbert RL. Adverse effects of hypolipidaemic drugs. Med Toxicol 1987;2:10-32. PubMed
- Guyton JR, Blazing MA, Hagar J, et al. Extended-release niacin vs gemfibrozil for the treatment of low levels of high-density lipoprotein cholesterol. Niaspan-Gemfibrozil Study Group. Arch Intern Med 2000;160:1177-84. PubMed
- Gibbons LW, Gonzalez V, Gordon N, Grundy S. The prevalence of side effects with regular and sustained-release nicotinic acid. Am J Med 1995;99:378-85. PubMed
- Whelan AM, Price SO, Fowler SF, Hainer BL. The effect of aspirin on niacin-induced cutaneous reactions. J Fam Pract 1992;34:165-8.
- Jungnickel PW, Maloley PA, Vander Tuin EL, et al. Effect of two aspirin pretreatment regimens on niacin-induced cutaneous reactions. J Gen Intern Med 1997;12:591-6. PubMed
- Capuzzi DM, Guyton JR, Morgan JM, et al. Efficacy and safety of an extended-release niacin (Niaspan): a long-term study. Am J Cardiol 1998;82:74-81;disc. 85U-6U. PubMed
- Gray DR, Morgan T, Chretien SD, Kashyap ML. Efficacy and safety of controlled-release niacin in dyslipoproteinemic veterans. Ann Intern Med 1994;121:252-8. PubMed
- McKenney JM, Proctor JD, Harris S, Chinchili VM. A comparison of the efficacy and toxic effects of sustained- vs immediate-release niacin in hypercholesterolemic patients. JAMA 1994;271:672-7. DOI
- Knopp RH, Alagona P, Davidson M, et al. Equivalent efficacy of a time-release form of niacin (Niaspan) given once-a-night versus plain niacin in the management of hyperlipidemia. Metabolism 1998;47:1097-104. PubMed
- Knopp RH. Clinical profiles of plain versus sustained-release niacin (Niaspan) and the physiologic rationale for nighttime dosing. Am J Cardiol 1998;82:24U-28U;discussion 39U-41U. PubMed
- Garg A, Grundy SM. Nicotinic acid as therapy for dyslipidemia in non-insulin-dependent diabetes mellitus. JAMA 1990;264:723-6. DOI
- Leighton RF, Gordon NF, Small GS, et al. Dental and gingival pain as side effects of niacin therapy. Chest 1998;114:1472-4. PubMed
- American Society of Health-System Pharmacists. ASHP Therapeutic Position Statement on the safe use of niacin in the management of dyslipidemias. Am J Health Syst Pharm 1997;54:2815-9. DOI
- Vega GL, Grundy SM. Lipoprotein responses to treatment with lovastatin, gemfibrozil, and nicotinic acid in normolipidemic patients with hypoalphalipoproteinemia. Arch Intern Med 1994;154:73-82. DOI
- Guyton JR, Goldberg AC, Kreisberg RA, et al. Effectiveness of once-nightly dosing of extended-release niacin alone and in combination for hypercholesterolemia. Am J Cardiol 1998;82:737-43.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Bays HE, Dujovne CA. Drug interactions of lipid-altering drugs. Drug Saf 1998;19:355-71. PubMed
- Rader JI, Calvert RJ, Hathcock JN. Hepatic toxicity of unmodified and time-release preparations of niacin. Am J Med 1992;92:77-81. PubMed
- Kahn SE, Beard JC, Schwartz MW, et al. Increased B-cell secretory capacity as mechanism for islet adaptation to nicotinic acid-induced insulin resistance. Diabetes 1989;38:562-8.
- Schwartz ML. Severe reversible hyperglycemia as a consequence of niacin therapy. Arch Int Med 1993;153:2050-2. DOI
- Raising HDL and Niacin Use. Pharmacist's Letter/Prescriber's Letter 2004;20(5):200504.
- McKenney J. New perspectives on the use of niacin in the treatment of lipid disorders. Arch Intern Med 2004;164:697-705. PubMed
- Reaven P, Witztum JL. Lovastatin, nicotinic acid and rhabdomyolysis (letter). Ann Int Med 1988;109:597-8. PubMed
- Ito MK. Advances in the understanding and management of dyslipidemia: using niacin-based therapies. Am J Health-Syst Pharm 2003;60(suppl 2):s15-21. PubMed
- Schwab RA, Bachhuber BH. Delirium and lactic acidosis caused by ethanol and niacin coingestion. Am J Emerg Med 1991;9:363-5. PubMed
- Product information: Niaspan. Kos Pharmaceuticals. Cranbury, NJ. 2005. Available at www.niaspan.com/professional/content/pdfs/productinfo.pdf. (Accessed 3 March 2006).
- Ding RW, Kolbe K, Merz B, et al. Pharmacokinetics of nicotinic acid-salicylic acid interaction. Clin Pharmacol Ther 1989;46:642-7. PubMed
- NIH News. NIH stops clinical trial on combination cholesterol treatment. May 26, 2011. http://www.nih.gov/news/health/may2011/nhlbi-26.htm. (Accessed 3 June 2011).
- Dearing BD, Lavie CJ, Lohmann TP, Genton E. Niacin-induced clotting factor synthesis deficiency with coagulopathy. Arch Intern Med. 1992;152(4):861-3. DOI
- O'Brien T, Silverberg JD, Nguyen TT. Nicotinic acid-induced toxicity associated with cytopenia and decreased levels of thyroxine-binding globulin. Mayo Clin Proc. 1992;67(5):465-8. PubMed
- Gadegbeku CA, Dhandayuthapani A, Shrayyef MZ, Egan BM. Hemodynamic effects of nicotinic acid infusion in normotensive and hypertensive subjects. Am J Hypertens. 2003;16(1):67-71. PubMed
- Garnett WR. Interactions with hydroxymethylglutaryl-coenzyme A reductase inhibitors. Am J Health Syst Pharm. 1995;52(15):1639-45. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Dunn RT, Ford MA, Rindone JP, Kwiecinski FA. Low-Dose Aspirin and Ibuprofen Reduce the Cutaneous Reactions Following Niacin Administration. Am J Ther. 1995;2(7):478-480. PubMed
- Cashin-Hemphill L, Spencer CA, Nicoloff JT, et al. Alterations in serum thyroid hormonal indices with colestipol-niacin therapy. Ann Intern Med. 1987;107(3):324-9. PubMed
- Drinka PJ. Alterations in thyroid and hepatic function tests associated with preparations of sustained-release niacin. Mayo Clin Proc. 1992;67(12):1206. PubMed
- Shakir KM, Kroll S, Aprill BS, Drake AJ 3rd, Eisold JF. Nicotinic acid decreases serum thyroid hormone levels while maintaining a euthyroid state. Mayo Clin Proc. 1995;70(6):556-8. PubMed
- Etchason JA, Miller TD, Squires RW, et al. Niacin-induced hepatitis: a potential side effect with low-dose time-release niacin. Mayo Clin Proc. 1991;66(1):23-8. PubMed
- Henkin Y, Johnson KC, Segrest JP. Rechallenge with crystalline niacin after drug-induced hepatitis from sustained-release niacin. JAMA. 1990;264(2):241-3. DOI
- Henkin Y, Oberman A, Hurst DC, Segrest JP. Niacin revisited: clinical observations on an important but underutilized drug. Am J Med. 1991;91(3):239-46. PubMed
- Brown BG, Bardsley J, Poulin D, et al. Moderate dose, three-drug therapy with niacin, lovastatin, and colestipol to reduce low-density lipoprotein cholesterol <100 mg/dl in patients with hyperlipidemia and coronary artery disease. Am J Cardiol. 1997;80(2)
- Goldberg A, Alagona P Jr, Capuzzi DM, et al. Multiple-dose efficacy and safety of an extended-release form of niacin in the management of hyperlipidemia. Am J Cardiol. 2000;85(9):1100-5. PubMed
- Aronov DM, Keenan JM, Akhmedzhanov NM, et al. Clinical trial of wax-matrix sustained-release niacin in a Russian population with hypercholesterolemia. Arch Fam Med. 1996;5(10):567-75. PubMed
- Morgan JM, Capuzzi DM, Guyton JR, et al. Treatment Effect of Niaspan, a Controlled-release Niacin, in Patients With Hypercholesterolemia: A Placebo-controlled Trial. J Cardiovasc Pharmacol Ther. 1996;1(3):195-202. PubMed
- Andersson RG, Aberg G, Brattsand R, Ericsson E, Lundholm L. Studies on the mechanism of flush induced by nicotinic acid. Acta Pharmacol Toxicol (Copenh). 1977 Jul;41(1):1-10. PubMed
- Brown WV. Niacin for lipid disorders. Indications, effectiveness, and safety. Postgrad Med. 1995 Aug;98(2):185-9, 192-3. PubMed
- O'REILLY PO, CALLBECK MJ, HOFFER A. Sustained-release nicotinic acid (nicospan); effect on (1) cholesterol levels and (2) leukocytes. Can Med Assoc J. 1959;80(5):359-62.
- Gharavi AG, Diamond JA, Smith DA, Phillips RA. Niacin-induced myopathy. Am J Cardiol. 1994;74(8):841-2. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Fraunfelder FW, Fraunfelder FT, Illingworth DR. Adverse ocular effects associated with niacin therapy. Br J Ophthalmol 1995;79:54-56. PubMed
- Ali EH, McJunkin B, Jubelirer S, Hood W. Niacin induced coagulopathy as a manifestation of occult liver injury. W V Med J. 2013 Jan-Feb;109(1):12-4
- Aramwit P, Srisawadwong R, Supasyndh O. Effectiveness and safety of extended-release nicotinic acid for reducing serum phosphorus in hemodialysis patients. J Nephrol. 2012 May-Jun;25(3):354-62. PubMed
- Bassan M. A case for immediate-release niacin. Heart Lung. 2012 Jan-Feb;41(1):95-8. PubMed
- Davidson MH, Rooney M, Pollock E, Drucker J, Choy Y. Effect of colesevelam and niacin on low-density lipoprotein cholesterol and glycemic control in subjects with dyslipidemia and impaired fasting glucose. J Clin Lipidol. 2013 Sep-Oct;7(5):423-32. PubMed
- Guyton JR, Fazio S, Adewale AJ, Jensen E, Tomassini JE, Shah A, Tershakovec AM. Effect of extended-release niacin on new-onset diabetes among hyperlipidemic patients treated with ezetimibe/simvastatin in a randomized controlled trial. Diabetes Care. 2012 PubMed
- Loebl T, Raskin S. A novel case report: acute manic psychotic episode after treatment with niacin. J Neuropsychiatry Clin Neurosci. 2013 Fall;25(4):E14. PubMed
- Teo KK, Goldstein LB, Chaitman BR, Grant S, Weintraub WS, Anderson DC, Sila CA, Cruz-Flores S, Padley RJ, Kostuk WJ, Boden WE; AIM-HIGH Investigators. Extended-release niacin therapy and risk of ischemic stroke in patients with cardiovascular disease: the
- Goldie C, Taylor AJ, Nguyen P, McCoy C, Zhao XQ, Preiss D. Niacin therapy and the risk of new-onset diabetes: a meta-analysis of randomized controlled trials. Heart. 2016 Feb;102(3):198-203.
- Schandelmaier S, Briel M, Saccilotto R, Olu KK, Arpagaus A, Hemkens LG, Nordmann AJ. Niacin for primary and secondary prevention of cardiovascular events. Cochrane Database Syst Rev. 2017 Jun 14;6:CD009744. PubMed
- Jenkins DJA, Spence JD, Giovannucci EL, et al. Supplemental vitamins and minerals for CVD prevention and treatment. J Am Coll Cardiol 2018;71(22):2570-84. PubMed
- Song S, Lee CJ, Oh J, Park S, Kang SM, Lee SH. Effect of Niacin on Carotid Atherosclerosis in Patients at Low-Density Lipoprotein-Cholesterol Goal but High Lipoprotein (a) Level: a 2-Year Follow-Up Study. J Lipid Atheroscler. 2019;8(1):58-66. PubMed
- Kimura H, Umemori Y, Yuki D. Anaphylactic shock-like symptoms due to niacin overdose: A case report. J Dermatol 2022;49(8):e287-e288. PubMed
- Nawaz N, Mistretta T, Karime C, Lewis J, Wolf E. Cholestatic Drug-Induced Liver Injury in a Patient Taking High-Dose Niacin for Hyperlipidemia. J Investig Med High Impact Case Rep 2024;12:23247096231224349. PubMed
Blessed Thistle 2 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
New Jersey Tea 1 reference
- Herbs at a Glance — NIH NCCIH Source
Greater Celandine 25 references
- Benninger J, Schneider HT, Schuppan D, et al. Acute hepatitis induced by greater celandine (Chelidonium majus). Gastroenterology 1999;117:1234-7. PubMed
- Holtmann G, Madisch A, Juergen H, et al. A double-blind, randomized, placebo-controlled trial on the effects of an herbal preparation in patients with functional dyspepsia [Abstract]. Ann Mtg Digestive Disease Week 1999 May.
- Madisch A, Holtmann G, Mayr G, et al. Treatment of functional dyspepsia with a herbal preparation. A double-blind, randomized, placebo-controlled, multicenter trial. Digestion 2004;69:45-52. PubMed
- Melzer J, Rosch W, Reichling J, et al. Meta-analysis: phytotherapy of functional dyspepsia with the herbal drug preparation STW 5 (Iberogast). Aliment Pharmacol Ther 2004;20:1279-87. PubMed
- Ernst E, Schmidt K. Ukrain - a new cancer cure? A systematic review of randomised clinical trials. BMC Cancer 2005;5:69. PubMed
- Stickel F, Poschl G, Seitz HK, et al. Acute hepatitis induced by Greater Celandine (Chelidonium majus). Scand J Gastroenterol 2003;38:565-8.
- Etxenagusia MA, Anda M, Gonzalez-Mahave I, et al. Contact dermatitis from Chelidonium majus (greater celandine). Contact Dermatitis 2000;43:47.
- Panzer A, Joubert AM, Bianchi PC, Seegers JC. The antimitotic effects of Ukrain, a Chelidonium majus alkaloid derivative, are reversible in vitro. Cancer Lett 2000;150:85-92. PubMed
- Moro PA, Cassetti F, Giugliano G, et al. Hepatitis from greater celandine (Chelidonium majus L.): Review of literature and report of a new case. J Ethnopharmacol 2009;124:328-32. PubMed
- Stickel, F., Seitz, H. K., Hahn, E. G., and Schuppan, D. [Liver toxicity of drugs of plant origin]. Z.Gastroenterol. 2001;39(3):225-227.
- Gansauge, F., Ramadani, M., Pressmar, J., Gansauge, S., Muehling, B., Stecker, K., Cammerer, G., Leder, G., and Beger, H. G. NSC-631570 (Ukrain) in the palliative treatment of pancreatic cancer. Results of a phase II trial. Langenbecks Arch.Surg. 2002;38 PubMed
- Nowicky, J. W., Manolakis, G., Meijer, D., Vatanasapt, V., and Brzosko, W. J. Ukrain both as an anti cancer and immunoregulatory agent. Drugs Exp.Clin Res 1992;18 Suppl:51-54.
- Staniszewski, A., Slesak, B., Kolodziej, J., Harlozinska-Szmyrka, A., and Nowicky, J. W. Lymphocyte subsets in patients with lung cancer treated with thiophosphoric acid alkaloid derivatives from Chelidonium majus L. (Ukrain). Drugs Exp.Clin Res 1992;18
- Nowicky, J. W., Staniszewski, A., Zbroja-Sontag, W., Slesak, B., Nowicky, W., and Hiesmayr, W. Evaluation of thiophosphoric acid alkaloid derivatives from Chelidonium majus L. ("Ukrain") as an immunostimulant in patients with various carcinomas. Drugs Ex
- Gansauge, F., Ramadani, M., Schwarz, M., Beger, H. G., Lotspeich, E., and Poch, B. The clinical efficacy of adjuvant systemic chemotherapy with gemcitabine and NSC-631570 in advanced pancreatic cancer. Hepatogastroenterology 2007;54(75):917-920.
- Hardeman, E., Van, Overbeke L., Ilegems, S., and Ferrante, M. Acute hepatitis induced by greater celandine (Chelidonium majus). Acta Gastroenterol.Belg. 2008;71(2):281-282.
- Gilca, M., Gaman, L., Panait, E., Stoian, I., and Atanasiu, V. Chelidonium majus--an integrative review: traditional knowledge versus modern findings. Forsch.Komplementmed. 2010;17(5):241-248. PubMed
- Teschke, R., Glass, X., and Schulze, J. Herbal hepatotoxicity by Greater Celandine (Chelidonium majus): causality assessment of 22 spontaneous reports. Regul.Toxicol.Pharmacol. 2011;61(3):282-291. PubMed
- Teschke, R., Glass, X., Schulze, J., and Eickhoff, A. Suspected Greater Celandine hepatotoxicity: liver-specific causality evaluation of published case reports from Europe. Eur.J Gastroenterol.Hepatol. 2012;24(3):270-280. PubMed
- Pinto, Garcia, V, Vicente, P. R., Barez, A., Soto, I., Candas, M. A., and Coma, A. [Hemolytic anemia induced by Chelidonium majus. Clinical case]. Sangre (Barc.) 1990;35(5):401-403.
- Teschke, R., Frenzel, C., Glass, X., Schulze, J., and Eickhoff, A. Greater Celandine hepatotoxicity: a clinical review. Ann.Hepatol. 2012;11(6):838-848. DOI
- Xian, M. S., Hayashi, K., Lu, J. P., and Awai, M. Efficacy of traditional Chinese herbs on squamous cell carcinoma of the esophagus: histopathologic analysis of 240 cases. Acta Med.Okayama 1989;43(6):345-351.
- Pantano F, Mannocchi G, Marinelli E, Gentili S, Graziano S, Busardò FP, di Luca NM. Hepatotoxicity induced by greater celandine (Chelidonium majus L.): a review of the literature. Eur Rev Med Pharmacol Sci. 2017 Mar;21(1 Suppl):46-52.
- Baek SC, Ryu HW, Kang MG, et al. Selective inhibition of monoamine oxidase A by chelerythrine, an isoquinoline alkaloid. Bioorg Med Chem Lett. 2018;28(14):2403-2407. PubMed
- Liu Y, Cui T, Peng Y, Ji M, Zheng J. Mechanism-based inactivation of cytochrome P450 2D6 by chelidonine. J Biochem Mol Toxicol. 2019;33(2):e22251. PubMed
Clubmoss 3 references
- Felgenhauer N, Zilker T, Worek F, Eyer P. Intoxication with huperzine A, a potent anticholinesterase found in the fir club moss. J Toxicol Clin Toxicol 2000;38:803-8.. PubMed
- Orhan, I., Terzioglu, S., and Sener, B. Alpha-onocerin: an acetylcholinesterase inhibitor from Lycopodium clavatum. Planta Med. 2003;69(3):265-267.
- Cullinan, P., Cannon, J., Sheril, D., and Newman, Taylor A. Asthma following occupational exposure to Lycopodium clavatum in condom manufacturers. Thorax 1993;48(7):774-775. PubMed
Sodium 38 references
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Food and Drug Administration Science Background: Safety of Sodium Phosphates Oral Solution. September 17, 2001. Available at: http://www.fda.gov/cder/drug/safety/sodiumphospate.htm
- Coton T, Mallaret C, Coilliot C, Carre D, Guisset M. Severe acute ulcerated gastritis induced by salt. Presse Med 2009;38(3):499-500. PubMed
- Frings-Meuthen P, Buehlmeier J, Baecker N, et al. High sodium chloride intake exacerbates immobilization-induced bone resorption and protein losses. J Appl Physiol 2011;111(2):537-542. PubMed
- Frings-Meuthen P, Baecker N, Heer M. Low-grade metabolic acidosis may be the cause of sodium chloride-induced exaggerated bone resorption. J Bone Miner Res 2008;23(4):517-524. PubMed
- Alam S, Johnson AG. A meta-analysis of randomised controlled trials (RCT) among healthy normotensive and essential hypertensive elderly patients to determine the effect of high salt (NaCl) diet of blood pressure. J Hum Hypertens 1999;13(6):367-74.
- Boudville N, Ward S, Benaroia M, House AA. Increased sodium intake correlates with greater use of antihypertensive agents by subjects with chronic kidney disease. Am J Hypertens 2005;18(10):1300-5. PubMed
- Bennett WM. Drug interactions and consequences of sodium restriction. Am J Clin Nutr 1997;65(2 Suppl):678S-681S. PubMed
- Okusa MD, Crystal LJ. Clinical manifestations and management of acute lithium intoxication. Am J Med 1994;97(4):383-9. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary reference intakes for water, potassium, sodium, chloride, and sulfate. Washington, DC: National Academy Press, 2005. Available at: http://www.nap.edu/openbook.php?record_id=10925. DOI
- D'Elia L, Rossi G, Ippolito R, Cappuccio FP, Strazzullo P. Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clin Nutr 2012;31(4):489-98. PubMed
- Goldsmith SR. Hyponatremia in heart failure: time for a trial. J Card Fail 2013;19(6):398-400. PubMed
- Willocks L, Brettle R, Keen J, Valentine C, Pinching AJ. Formulations of didanosine (ddI) and salt overload. Lancet 1992;339(8786):190.
- Chen L, Zhang Z, Chen W, Whelton PK, Appel LJ. Lower Sodium Intake and Risk of Headaches: Results From the Trial of Nonpharmacologic Interventions in the Elderly. Am J Public Health. 2016;106(7):1270-5. PubMed
- Cook NR, Appel LJ, Whelton PK. Lower levels of sodium intake and reduced cardiovascular risk. Circulation. 2014;129(9):981-9. PubMed
- Cook NR, Appel LJ, Whelton PK. Sodium Intake and All-Cause Mortality Over 20 Years in the Trials of Hypertension Prevention. J Am Coll Cardiol. 2016;68(15):1609-1617. PubMed
- Mente A, O'Donnell M, Rangarajan S, et al. Associations of urinary sodium excretion with cardiovascular events in individuals with and without hypertension: a pooled analysis of data from four studies. Lancet. 2016;388(10043):465-75. PubMed
- Moosavian SP, Haghighatdoost F, Surkan PJ, Azadbakht L. Salt and obesity: a systematic review and meta-analysis of observational studies. Int J Food Sci Nutr. 2017;68(3):265-277. PubMed
- O'Donnell M, Mente A, Rangarajan S, et al. Urinary sodium and potassium excretion, mortality, and cardiovascular events. N Engl J Med. 2014;371(7):612-23. DOI
- Poggio R, Gutierrez L, Matta MG, Elorriaga N, Irazola V, Rubinstein A. Daily sodium consumption and CVD mortality in the general population: systematic review and meta-analysis of prospective studies. Public Health Nutr. 2015;18(4):695-704. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Mahtani KR, Heneghan C, Onakpoya I, et al. Reduced Salt Intake for Heart Failure: A Systematic Review. JAMA Intern Med. 2018 Dec 1;178(12):1693-1700. PubMed
- Yancy CW. Sodium Restriction in Heart Failure: Too Much Uncertainty-Do the Trials. JAMA Intern Med. 2018 Dec 1;178(12):1700-1701. PubMed
- He FJ, Campbell NRC, Ma Y, MacGregor GA, Cogswell ME, Cook NR. Errors in estimating usual sodium intake by the Kawasaki formula alter its relationship with mortality: implications for public health. Int J Epidemiol. 2018;47(6):1784-1795. PubMed
- Murthy K, Ondrey GJ, Malkani N, et al. THE EFFECTS OF HYPONATREMIA ON BONE DENSITY AND FRACTURES: A SYSTEMATIC REVIEW AND META-ANALYSIS. Endocr Pract. 2019;25(4):366-378. PubMed
- Messerli FH, Hofstetter L, Syrogiannouli L, et al. Sodium intake, life expectancy, and all-cause mortality. Eur Heart J 2021;42(21):2103-2112. PubMed
- Graudal NA, Hubeck-Graudal T, Jurgens G. Effects of low sodium diet versus high sodium diet on blood pressure, renin, aldosterone, catecholamines, cholesterol, and triglyceride. Cochrane Database Syst Rev 2020;12(12):CD004022. PubMed
- Giatti S, Santos RB, Aielo AN, et al. Association of sodium with obstructive sleep apnea. The ELSA-Brasil study. Ann Am Thorac Soc 2021;18(3):502-510. PubMed
- Nan X, Lu H, Wu J, et al. The interactive association between sodium intake, alcohol consumption and hypertension among elderly in northern China: a cross-sectional study. BMC Geriatr 2021;21(1):135. PubMed
- Kyozuka H, Fukusda T, Murata T, et al. Impact of preconception sodium intake on hypertensive disorders of pregnancy: The Japan Environment and Children's study. Pregnancy Hypertens 2021;23:66-72. PubMed
- Zhao L, Ogden CL, Yang Q, et al. Association of usual sodium intake with obesity among US children and adolescents, NHANES 2009-2016. Obesity (Silver Spring) 2021;29(3):587-594. PubMed
- Ma Y, He FJ, Sun Q, et al. 24-Hour urinary sodium and potassium excretion and cardiovascular risk. N Engl J Med 2022;386(3):252-263. PubMed
- Liu J, Yang X, Zhang P, et al. Association of urinary sodium excretion and left ventricular hypertrophy in people with type 2 diabetes mellitus: A cross-sectional study. Front Endocrinol (Lausanne) 2021;12:728493. PubMed
- Filippini T, Malavolti M, Whelton PK, Vinceti M. Sodium intake and risk of hypertension: A systematic review and dose-response meta-analysis of observational cohort studies. Curr Hypertens Rep 2022;24(5):133-144. PubMed
- Wang DD, Li Y, Nguyen XT, et al. Dietary sodium and potassium intake and risk of non-fatal cardiovascular diseases: The million veteran program. Nutrients 2022;14(5):1121. PubMed
- Kwak JH, Park CH, Eun CS, et al. The associations of dietary intake of high sodium and low zinc with gastric cancer mortality: A prospective cohort study in Korea. Nutr Cancer 2022;74(10):3501-3508. PubMed
- George S, Maiti R, Mishra BR, Jena M, Mohapatra D. Effect of regulated add-on sodium chloride intake on stabilization of serum lithium concentration in bipolar disorder: A randomized controlled trial. Bipolar Disord 2023;25(1):66-75. PubMed
- Zhou TL, Schütten MTJ, Kroon AA, et al. Urinary Sodium Excretion and Salt Intake Are Not Associated With Blood Pressure Variability in a White General Population. J Am Heart Assoc 2023;12(1):e026578. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC