
Whey Sport Vanilla Ingredients & Drug Interactions
by Cellucor
What is this page for?
First and foremost: checking Whey Sport Vanilla against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Whey Sport Vanilla is a dietary supplement by Cellucor with 9 active ingredients. Its ingredients are commonly taken for muscle recovery and sports performance, gut health and 'leaky gut', recovery from severe illness or injury.Based on those ingredients, 536 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Vitamin C, Sodium, Calcium. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Whey Sport Vanilla by Cellucor
Ask about any prescription or over-the-counter medication and we check it for interactions with Whey Sport Vanilla by Cellucor — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Whey Sport Vanilla by Cellucor
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Partial disclosure
Whey Sport Vanilla contains 7 active ingredients. L-glutamine is an amino acid involved in immune and muscle health; sodium is an electrolyte; vitamin C supports collagen and immune function; calcium builds and maintains bone; whey protein concentrate and whey protein isolate are fast-absorbing muscle-building proteins; and creatine monohydrate supports muscle strength and energy production during intense exercise.
The product also includes inactive ingredients—cellulose gum, xanthan gum, natural and artificial flavors, protease enzymes, sweeteners (acesulfame potassium and sucralose), and lactase—which serve as thickeners, flavorings, and digestive aids.
Does it work?
Moderate evidence
Evidence exists for several uses. Calcium is effective for osteoporosis and hypocalcemia.
Whey protein is possibly effective for athletic performance. Vitamin C is effective for vitamin C deficiency and possibly effective for anemia and some infections.
L-glutamine is effective for sickle cell disease and possibly effective for HIV/AIDS-related wasting and post-operative recovery. Creatine monohydrate is possibly effective for muscle strength and athletic performance.
For other claimed uses in this product, the evidence we hold is either insufficient or shows the ingredient is possibly ineffective.
How safe is it?
Well-documented data
This product is generally well tolerated in healthy adults. Calcium, sodium, and vitamin C are generally safe at recommended amounts, though high doses of vitamin C can cause diarrhea, nausea, and kidney stones in those prone to them.
L-glutamine is generally well tolerated but should be used only under medical supervision in people with kidney or liver disease. Whey protein commonly causes bloating, cramps, diarrhea, nausea, and reflux; multiple case reports associate it with acne, especially in young adults.
Creatine monohydrate may cause dehydration, muscle cramps, and water retention. Sodium in high amounts raises blood pressure and strains the heart and kidneys—normal dietary amounts are fine, but this product's contribution should be considered if you're watching sodium intake.
For pregnancy: L-glutamine, calcium, and vitamin C are rated likely safe; creatine safety has not been established and should be avoided; and safety data for whey protein during pregnancy is not on file, so speak with your doctor. For breastfeeding: L-glutamine, calcium, and vitamin C safety data is not fully established—speak with your clinician; whey protein and creatine safety data during lactation is not on file.
Meds to double-check
Major interaction found
Before taking Whey Sport Vanilla, double-check these medication types with your pharmacist: HIV integrase inhibitors (dolutegravir, elvitegravir) because calcium sharply reduces their blood levels; levodopa for Parkinson disease because whey protein may worsen symptoms; anticonvulsants because L-glutamine theoretically antagonizes them; antihypertensive drugs because sodium may reduce their effect; lithium because sodium changes can cause toxicity; warfarin because vitamin C at high doses reduces its effect; quinolone and tetracycline antibiotics because whey protein's minerals block absorption; and bisphosphonate bone medications because calcium interferes with their uptake. No interactions are documented in our data for creatine monohydrate.
The bottom line
Scorecard at a glancePartially disclosed formula with some supporting evidence for its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
Whey Sport Vanilla is a multi-purpose protein and supplement powder best suited for healthy adults doing strength training or managing athletic recovery. If you take HIV medications (integrase inhibitors), Parkinson's treatments, blood pressure drugs, lithium, warfarin, antibiotics, bone medications, or any other regular medication, check your exact drugs with the tool on this page before adding this product.
Those with kidney disease, high blood pressure, or a history of kidney stones should talk with their pharmacist first.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 7 of 7 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated May 23, 2024.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Whey Sport Vanilla, straight from the product label.
| Brand | Cellucor |
|---|---|
| Net contents | 837 Gram(s); 29.5 Ounce(s) |
| Market status | On market |
| Date entered into DSLD | May 23, 2024 |
| DSLD ID | 309674 |
| Product type | Other Combinations |
| Supplement form | Powder |
| Dietary claims / uses | Nutrient, All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Gluten Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
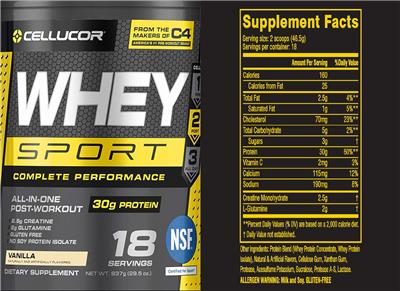
Supplement Facts
The label details for Whey Sport Vanilla by Cellucor, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Calories | 160 Calorie(s) | -- |
| Total Carbohydrates | 5 Gram(s) | 2% |
| L-Glutamine | 2 Gram(s) | -- |
| Sugar | 3 Gram(s) | -- |
| Calories from Fat | 25 Calorie(s) | -- |
| Sodium | 190 mg | 8% |
| Vitamin C | 2 mg | 3% |
| Calcium | 115 mg | 12% |
| Cholesterol | 70 mg | 23% |
| Total Fat | 2.5 Gram(s) | 4% |
| Saturated Fat | 1 Gram(s) | 5% |
| Protein | 30 Gram(s) | 60% |
| Whey Protein Concentrate | 0 NP | -- |
| Whey Protein Isolate | 0 NP | -- |
| Creatine Monohydrate | 2.5 Gram(s) | -- |
Other ingredients: Natural & Artificial Flavors, Cellulose Gum, Xanthan Gum, Protease, Acesulfame Potassium, Sucralose, Protease A-S, Lactase
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
General Statements
From the makers of C4 America's #1 pre-workout brand
Formulation
Complete performance All-in-one post workout 1 Pre 2 Post 3 All day
Gluten-free No soy protein isolate
Formula
30 g protein 2.5 g creatine 2 g glutamine Vanilla naturally and artificially flavored
FDA Statement of Identity
Dietary Supplement
Seals/Symbols
NSF Certified for Sport
Precautions
Allergen warning: Milk and soy.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Whey Sport Vanilla by Cellucor label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Whey Sport Vanilla by Cellucor
These are the 9 active ingredients this product is made of. Select any to open its full monograph.
Serving size46.5 Gram(s) Dosage formPowder Servings per container18 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
L-Glutamine
Interacts with50 drugs
Glutamine is the most abundant amino acid in the body and is usually made in your muscles. A prescription form is FDA-approved to help reduce sickle c...
L-Glutamine monograph & interactionsSugar
Sodium
Interacts with205 drugs
Sodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets g...
Sodium monograph & interactionsVitamin C
Interacts with207 drugs
Vitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for im...
Vitamin C monograph & interactionsCalcium
Interacts with168 drugs
Calcium is an essential mineral your body needs for strong bones, nerve signaling, and muscle function, and supplements can help fill gaps when diet f...
Calcium monograph & interactionsProtein
Whey Protein Concentrate
Interacts with53 drugs
Whey protein is a high-quality, complete protein made from cow's milk that can help people meet protein needs and support muscle growth when combined...
Whey Protein Concentrate monograph & interactionsWhey Protein Isolate
Interacts with53 drugs
Whey protein is a high-quality, complete protein made from cow's milk that can help people meet protein needs and support muscle growth when combined...
Whey Protein Isolate monograph & interactionsCreatine Monohydrate
No knowninteractions
Creatine is one of the most studied sports supplements, with solid evidence that it can boost strength and performance during short, high-intensity ac...
Creatine Monohydrate monograph & interactionsOther (inactive) ingredients: Natural & Artificial Flavors, Cellulose Gum, Xanthan Gum, Protease, Acesulfame Potassium, Sucralose, Protease A-S, Lactase. These complete the product’s ingredient list but are not active constituents.
Whey Sport Vanilla by Cellucor Drug Interactions
HelloPharmacist Interaction Report
Whey Sport Vanilla by Cellucor does interact with medications across several drug classes, with the most serious concerns involving HIV integrase inhibitors and Parkinson's treatments.
Calcium in this product significantly reduces levels of dolutegravir and elvitegravir (HIV medications)—by nearly 40% and through chelation, respectively—requiring a 2–6 hour separation between doses. Whey protein itself may theoretically interfere with levodopa, worsening tremor and rigidity in Parkinson disease.
Read the full breakdown — every affected drug type, severity by severity
Sodium in this product has documented Moderate interactions with antihypertensive drugs (blood pressure medications), corticosteroids, lithium, didanosine, sodium phosphates, tolvaptan, and other sodium-containing drugs. High sodium can reduce the effectiveness of blood pressure medications or increase lithium toxicity risk if dietary sodium varies.
Vitamin C interacts with estrogens (increasing blood levels up to 55%), alkylating agents used in chemotherapy, aluminum, warfarin (blood thinner), and several other drugs, with most interactions rated Moderate. L-glutamine theoretically antagonizes anticonvulsant medications, though this hasn't been documented in humans.
The whey proteins also interact with quinolone and tetracycline antibiotics, as well as bisphosphonates (bone medications), because calcium in whey binds these drugs and reduces absorption. Creatine monohydrate shows no documented interactions in our data.
Altogether, these interactions span 533 individual medications.
Use the medication checker on this page to search your exact drugs before taking this product.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Whey Sport Vanilla?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Whey Sport Vanilla interact with 536 drugs. Click any drug to see the details.
5 of the 9 ingredients in Whey Sport Vanilla interact with drugs. Each result below shows which ingredient is responsible. Vitamin C Sodium Calcium Whey Protein Concentrate L-Glutamine
Benserazide, LevodopaMadopar, Prolopa
How Benserazide, Levodopa interacts with Whey Sport Vanilla — through 1 ingredient. Tap an ingredient for the detail:
Whey Protein IsolateLevodopa Major
Interaction Summary
Theoretically, whey protein might decrease levodopa absorption.
Read the full Whey Protein Isolate + Benserazide, Levodopa interactionCarbidopa, LevodopaDhivy, Rytary, Sinemet, Sinemet CR
How Carbidopa, Levodopa interacts with Whey Sport Vanilla — through 1 ingredient. Tap an ingredient for the detail:
Whey Protein IsolateLevodopa Major
Interaction Summary
Theoretically, whey protein might decrease levodopa absorption.
Read the full Whey Protein Isolate + Carbidopa, Levodopa interactionCarbidopa, Levodopa, EntacaponeStalevo
How Carbidopa, Levodopa, Entacapone interacts with Whey Sport Vanilla — through 1 ingredient. Tap an ingredient for the detail:
Whey Protein IsolateLevodopa Major
Interaction Summary
Theoretically, whey protein might decrease levodopa absorption.
Read the full Whey Protein Isolate + Carbidopa, Levodopa, Entacapone interactionCeftriaxoneRocephin
How Ceftriaxone interacts with Whey Sport Vanilla — through 1 ingredient. Tap an ingredient for the detail:
CalciumCeftriaxone (rocephin) Major
Interaction Summary
Co-administration of intravenous calcium and ceftriaxone can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys.
Read the full Calcium + Ceftriaxone interactionCobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide FumarateGenvoya
How Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interacts with Whey Sport Vanilla — through 1 ingredient. Tap an ingredient for the detail:
CalciumElvitegravir (vitekta), Bictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Major
Interaction Summary
Calcium seems to reduce levels of elvitegravir.
Read the full Calcium + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionDolutegravirTivicay
How Dolutegravir interacts with Whey Sport Vanilla — through 1 ingredient. Tap an ingredient for the detail:
CalciumDolutegravir (tivicay) Major
Interaction Summary
Calcium seems to reduce levels of dolutegravir.
Read the full Calcium + Dolutegravir interactionDolutegravir, Emtricitabine, Tenofovir AlafenamideDolutegravir, Emtricitabine, Tenofovir Alafenamide
How Dolutegravir, Emtricitabine, Tenofovir Alafenamide interacts with Whey Sport Vanilla — through 1 ingredient. Tap an ingredient for the detail:
CalciumDolutegravir (tivicay), Bictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Major
Interaction Summary
Calcium seems to reduce levels of dolutegravir.
Read the full Calcium + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionDolutegravir, RilpivirineJuluca
How Dolutegravir, Rilpivirine interacts with Whey Sport Vanilla — through 1 ingredient. Tap an ingredient for the detail:
CalciumDolutegravir (tivicay) Major
Interaction Summary
Calcium seems to reduce levels of dolutegravir.
Read the full Calcium + Dolutegravir, Rilpivirine interactionElvitegravirVitekta
How Elvitegravir interacts with Whey Sport Vanilla — through 1 ingredient. Tap an ingredient for the detail:
CalciumElvitegravir (vitekta) Major
Interaction Summary
Calcium seems to reduce levels of elvitegravir.
Read the full Calcium + Elvitegravir interactionElvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil FumarateStribild
How Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interacts with Whey Sport Vanilla — through 1 ingredient. Tap an ingredient for the detail:
CalciumElvitegravir (vitekta), Bictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Major
Interaction Summary
Calcium seems to reduce levels of elvitegravir.
Read the full Calcium + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionLevodopaInbrija, Larodopa
How Levodopa interacts with Whey Sport Vanilla — through 1 ingredient. Tap an ingredient for the detail:
Whey Protein IsolateLevodopa Major
Interaction Summary
Theoretically, whey protein might decrease levodopa absorption.
Read the full Whey Protein Isolate + Levodopa interactionLevodopa, CarbidopaDuodopa
How Levodopa, Carbidopa interacts with Whey Sport Vanilla — through 1 ingredient. Tap an ingredient for the detail:
Whey Protein IsolateLevodopa Major
Interaction Summary
Theoretically, whey protein might decrease levodopa absorption.
Read the full Whey Protein Isolate + Levodopa, Carbidopa interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Whey Sport Vanilla — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Acebutolol interactionAcetazolamideAk-Zol, Diamox
How Acetazolamide interacts with Whey Sport Vanilla — through 2 ingredients. Tap an ingredient for the detail:
L-glutamineAnticonvulsants Moderate
Interaction Summary
Theoretically, glutamine might antagonize the effects of anticonvulsant medications.
Read the full L-glutamine + Acetazolamide interactionSodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Acetazolamide interactionAlendronateBinosto, Fosamax
How Alendronate interacts with Whey Sport Vanilla — through 2 ingredients. Tap an ingredient for the detail:
CalciumBisphosphonates Moderate
Interaction Summary
Calcium reduces the absorption of bisphosphonates.
Read the full Calcium + Alendronate interactionWhey Protein IsolateBisphosphonates Moderate
Interaction Summary
Theoretically, whey protein might reduce the absorption of bisphosphonates.
Read the full Whey Protein Isolate + Alendronate interactionAlendronate Sodium
How Alendronate Sodium interacts with Whey Sport Vanilla — through 2 ingredients. Tap an ingredient for the detail:
CalciumBisphosphonates Moderate
Interaction Summary
Calcium reduces the absorption of bisphosphonates.
Read the full Calcium + Alendronate Sodium interactionWhey Protein IsolateBisphosphonates Moderate
Interaction Summary
Theoretically, whey protein might reduce the absorption of bisphosphonates.
Read the full Whey Protein Isolate + Alendronate Sodium interactionAlendronate Sodium, CholecalciferolFosamax Plus D
How Alendronate Sodium, Cholecalciferol interacts with Whey Sport Vanilla — through 2 ingredients. Tap an ingredient for the detail:
CalciumBisphosphonates Moderate
Interaction Summary
Calcium reduces the absorption of bisphosphonates.
Read the full Calcium + Alendronate Sodium, Cholecalciferol interactionWhey Protein IsolateBisphosphonates Moderate
Interaction Summary
Theoretically, whey protein might reduce the absorption of bisphosphonates.
Read the full Whey Protein Isolate + Alendronate Sodium, Cholecalciferol interactionAlginic Acid, Aluminum HydroxideRafton
How Alginic Acid, Aluminum Hydroxide interacts with Whey Sport Vanilla — through 2 ingredients. Tap an ingredient for the detail:
CalciumAluminum Moderate
Interaction Summary
Calcium citrate might increase aluminum absorption and toxicity.
Read the full Calcium + Alginic Acid, Aluminum Hydroxide interactionVitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Alginic Acid, Aluminum Hydroxide interactionAliskirenTekturna
How Aliskiren interacts with Whey Sport Vanilla — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Aliskiren interactionAltretamineHexalen
How Altretamine interacts with Whey Sport Vanilla — through 1 ingredient. Tap an ingredient for the detail:
Vitamin CAlkylating Agents Moderate
Interaction Summary
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
Read the full Vitamin C + Altretamine interactionAluminum Acetate, Benzethonium ChlorideBuro-Sol Otic Solution
How Aluminum Acetate, Benzethonium Chloride interacts with Whey Sport Vanilla — through 2 ingredients. Tap an ingredient for the detail:
Vitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum Acetate, Benzethonium Chloride interactionCalciumAluminum Moderate
Interaction Summary
Calcium citrate might increase aluminum absorption and toxicity.
Read the full Calcium + Aluminum Acetate, Benzethonium Chloride interactionAluminum ChlorideAluminum Chloride, Anhydrol Forte, Driclor, Drysol
How Aluminum Chloride interacts with Whey Sport Vanilla — through 2 ingredients. Tap an ingredient for the detail:
CalciumAluminum Moderate
Interaction Summary
Calcium citrate might increase aluminum absorption and toxicity.
Read the full Calcium + Aluminum Chloride interactionVitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum Chloride interactionAluminum HydroxideAlu-Cap, Amphojel, Gaviscon
How Aluminum Hydroxide interacts with Whey Sport Vanilla — through 2 ingredients. Tap an ingredient for the detail:
Vitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum Hydroxide interactionCalciumAluminum Moderate
Interaction Summary
Calcium citrate might increase aluminum absorption and toxicity.
Read the full Calcium + Aluminum Hydroxide interactionAluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium HydroxideAscriptin Codeine #2
How Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interacts with Whey Sport Vanilla — through 2 ingredients. Tap an ingredient for the detail:
CalciumAluminum Moderate
Interaction Summary
Calcium citrate might increase aluminum absorption and toxicity.
Read the full Calcium + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionVitamin CAspirin, Aluminum Moderate
Interaction Summary
Acidification of the urine by vitamin C might increase aspirin levels.
Read the full Vitamin C + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionAluminum Hydroxide, Aspirin, Magnesium HydroxideAscriptin
How Aluminum Hydroxide, Aspirin, Magnesium Hydroxide interacts with Whey Sport Vanilla — through 2 ingredients. Tap an ingredient for the detail:
Vitamin CAluminum, Aspirin Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum Hydroxide, Aspirin, Magnesium Hydroxide interactionCalciumAluminum Moderate
Interaction Summary
Calcium citrate might increase aluminum absorption and toxicity.
Read the full Calcium + Aluminum Hydroxide, Aspirin, Magnesium Hydroxide interactionAluminum Hydroxide, Magnesium Hydroxide (otc Drug)Maalox, Mucogel
How Aluminum Hydroxide, Magnesium Hydroxide (otc Drug) interacts with Whey Sport Vanilla — through 2 ingredients. Tap an ingredient for the detail:
Vitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum Hydroxide, Magnesium Hydroxide (otc Drug) interactionCalciumAluminum Moderate
Interaction Summary
Calcium citrate might increase aluminum absorption and toxicity.
Read the full Calcium + Aluminum Hydroxide, Magnesium Hydroxide (otc Drug) interactionAluminum Hydroxide, Magnesium Hydroxide, Simethicone (otc Drug)Mylanta
How Aluminum Hydroxide, Magnesium Hydroxide, Simethicone (otc Drug) interacts with Whey Sport Vanilla — through 2 ingredients. Tap an ingredient for the detail:
CalciumAluminum Moderate
Interaction Summary
Calcium citrate might increase aluminum absorption and toxicity.
Read the full Calcium + Aluminum Hydroxide, Magnesium Hydroxide, Simethicone (otc Drug) interactionVitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum Hydroxide, Magnesium Hydroxide, Simethicone (otc Drug) interactionAluminum, CalciumDomeboro
How Aluminum, Calcium interacts with Whey Sport Vanilla — through 2 ingredients. Tap an ingredient for the detail:
Vitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum, Calcium interactionCalciumAluminum Moderate
Interaction Summary
Calcium citrate might increase aluminum absorption and toxicity.
Read the full Calcium + Aluminum, Calcium interactionAluminum, Magnesium (otc Drug)Almagel
How Aluminum, Magnesium (otc Drug) interacts with Whey Sport Vanilla — through 2 ingredients. Tap an ingredient for the detail:
CalciumAluminum Moderate
Interaction Summary
Calcium citrate might increase aluminum absorption and toxicity.
Read the full Calcium + Aluminum, Magnesium (otc Drug) interactionVitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum, Magnesium (otc Drug) interactionAluminum, Magnesium Hydroxide (otc Drug)Wingel
How Aluminum, Magnesium Hydroxide (otc Drug) interacts with Whey Sport Vanilla — through 2 ingredients. Tap an ingredient for the detail:
Vitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum, Magnesium Hydroxide (otc Drug) interactionCalciumAluminum Moderate
Interaction Summary
Calcium citrate might increase aluminum absorption and toxicity.
Read the full Calcium + Aluminum, Magnesium Hydroxide (otc Drug) interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Whey Sport Vanilla with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Vitamin C
Alkylating Agents
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin C have on chemotherapy.
Aluminum
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Research in animals and humans shows that vitamin C increases aluminum absorption, theoretically by chelating aluminum and keeping it in solution where it is available for absorption. In people with normal renal function, urinary excretion of aluminum will likely increase, making aluminum retention and toxicity unlikely. Patients with renal failure who take aluminum-containing compounds such as phosphate binders should avoid vitamin C supplements in doses above the recommended dietary allowances.
Antitumor Antibiotics
Theoretically, the antioxidant effects of vitamin C might reduce the effectiveness of antitumor antibiotics.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as doxorubicin. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effects, if any, antioxidants such as vitamin C have on chemotherapy.
Estrogens
Vitamin C might increase blood levels of estrogens.
Increases in plasma estrogen levels of up to 55% occur under some circumstances when vitamin C is taken concurrently with oral contraceptives or hormone replacement therapy, including topical products. It is suggested that vitamin C prevents oxidation of estrogen in the tissues, regenerates oxidized estrogen, and reduces sulfate conjugation of estrogen in the gut wall. When tissue levels of vitamin C are high, these processes are already maximized and supplemental vitamin C does not have any effect on estrogen levels. Increases in plasma estrogen levels may occur when patients who are deficient in vitamin C take supplements. Monitor these patients for estrogen-related side effects.
Fluphenazine (Prolixin)
Theoretically, vitamin C might decrease levels of fluphenazine.
In one patient there was a clinically significant decrease in fluphenazine levels when vitamin C (500 mg twice daily) was started. The mechanism is not known, and there is no further data to confirm this interaction.
Indinavir (Crixivan)
Vitamin C can modestly reduce indinavir levels.
One pharmacokinetic study shows that taking vitamin C 1 gram orally once daily along with indinavir 800 mg orally three times daily reduces the area under the concentration-time curve of indinavir by 14%. The mechanism of this interaction is unknown, but it is unlikely to be clinically significant in most patients. The effect of higher doses of vitamin C on indinavir levels is unknown.
Levothyroxine (Synthroid, Others)
Vitamin C can increase levothyroxine absorption.
Two clinical studies in adults with poorly controlled hypothyroidism show that swallowing levothyroxine with a glass of water containing vitamin C 500-1000 mg in solution reduces thyroid stimulating hormone (TSH) levels and increases thyroxine (T4) levels when compared with taking levothyroxine alone. This suggests that vitamin C increases the oral absorption of levothyroxine, possibly due to a reduction in pH.
Warfarin (Coumadin)
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Vitamin C in high doses may cause diarrhea and possibly reduce warfarin absorption. There are reports of two people who took up to 16 grams daily of vitamin C and had a reduction in prothrombin time. Lower doses of 5-10 grams daily can also reduce warfarin absorption. In many cases, this does not seem to be clinically significant. However, a case of warfarin resistance has been reported for a patient who took vitamin C 500 mg twice daily. Cessation of vitamin C supplementation resulted in a rapid increase in international normalized ratio (INR). Tell patients taking warfarin to avoid taking vitamin C in excessively high doses (greater than 10 grams daily). Lower doses may be safe, but the anticoagulation activity of warfarin should be monitored. Patients who are stabilized on warfarin while taking vitamin C should avoid adjusting vitamin C dosage to prevent the possibility of warfarin resistance.
Acetaminophen (Tylenol, Others)
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
A small pharmacokinetic study in healthy volunteers shows that taking high-dose vitamin C (3 grams) 1.5 hours after taking acetaminophen 1 gram slightly increases the apparent half-life of acetaminophen from around 2.3 hours to 3.1 hours. Ascorbic acid competitively inhibits sulfate conjugation of acetaminophen. However, to compensate, elimination of acetaminophen glucuronide and unconjugated acetaminophen increases. This effect is not likely to be clinically significant.
Aspirin
Acidification of the urine by vitamin C might increase aspirin levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction is not clinically significant.
Choline Magnesium Trisalicylate (Trilisate)
Acidification of the urine by vitamin C might increase choline magnesium trisalicylate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Niacin
Vitamin C might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as vitamin C, or to the combination. It also is not known whether it will occur in other patient populations.
Salsalate (Disalcid)
Acidification of the urine by vitamin C might increase salsalate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams/day vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Sodium
Antihypertensive Drugs
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
High intake of dietary sodium can increase systolic and diastolic blood pressure. Also, high intake of sodium may necessitate increased use of antihypertensive medications to achieve blood pressure control in some patients, such as those with chronic kidney disease.
Corticosteroids
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Mineralocorticoids and some glucocorticoids (corticosteroids) cause sodium retention. This effect is dose-related and depends on mineralocorticoid potency. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Didanosine (Videx)
Concomitant use of didanosine with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia.
Didanosine formulations contain a significant amount of sodium.
Lithium
Altering dietary intake of sodium might alter the levels and clinical effects of lithium.
High sodium intake can reduce plasma concentrations of lithium by increasing lithium excretion. Reducing sodium intake can significantly increase plasma concentrations of lithium and cause lithium toxicity in patients being treated with lithium carbonate. Stabilizing sodium intake is shown to reduce the percentage of patients with lithium level fluctuations above 0.8 mEq/L. Patients taking lithium should avoid significant alterations in their dietary intake of sodium.
Sodium Phosphates
Theoretically, concomitant use of sodium phosphate with sodium supplements might increase the risk of hypernatremia.
Use of high doses (> 45 mL in 24 hours) of sodium phosphate, such as those used for bowel cleansing before surgery, can lead to serious electrolyte disturbances, including hypernatremia. The risk of hypernatremia is highest in the elderly and people with other risk factors for electrolyte disturbances.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related complications.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium supplements or high-sodium diets, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Tolvaptan (Samsca)
Theoretically, concomitant use of tolvaptan with sodium might increase the risk of hypernatremia.
Tolvaptan is a vasopressin receptor 2 antagonist that is used to increase sodium levels in patients with hyponatremia. Patients taking tolvaptan should use caution with the use of sodium salts such as sodium chloride.
Calcium
Ceftriaxone (Rocephin)
Co-administration of intravenous calcium and ceftriaxone can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys.
Avoid administering intravenous calcium in any form, such as parenteral nutrition or Lactated Ringers, within 48 hours of intravenous ceftriaxone. Case reports in neonates show that administering intravenous ceftriaxone and calcium can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys. In several cases, neonates have died as a result of this interaction. So far there are no reports in adults; however, there is still concern that this interaction might occur in adults.
Dolutegravir (Tivicay)
Calcium seems to reduce levels of dolutegravir.
Advise patients to take dolutegravir either 2 hours before or 6 hours after taking calcium supplements. Pharmacokinetic research suggests that taking calcium carbonate 1200 mg concomitantly with dolutegravir 50 mg reduces plasma levels of dolutegravir by almost 40%. Calcium appears to decrease levels of dolutegravir through chelation.
Elvitegravir (Vitekta)
Calcium seems to reduce levels of elvitegravir.
Advise patients to take elvitegravir either 2 hours before or 2 hours after taking calcium supplements. Pharmacokinetic research suggests that taking calcium along with elvitegravir can reduce blood levels of elvitegravir through chelation.
Aluminum
Calcium citrate might increase aluminum absorption and toxicity. Other types of calcium do not increase aluminum absorption.
Calcium citrate can increase the absorption of aluminum when taken with aluminum hydroxide. The increase in aluminum levels may become toxic, particularly in individuals with kidney disease. However, the effect of calcium citrate on aluminum absorption is due to the citrate anion rather than calcium cation. Calcium acetate does not appear to increase aluminum absorption.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Calcium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide and calcium can be taken together if taken with food. However, if taken on an empty stomach, bictegravir/emtricitabine/tenofovir alafenamide should not be taken with, or 2 hours after, calcium containing products.
Bisphosphonates
Calcium reduces the absorption of bisphosphonates.
Advise patients to take bisphosphonates at least 30 minutes before calcium, but preferably at a different time of day. Calcium supplements decrease absorption of bisphosphonates.
Calcipotriene (Dovonex)
Taking calcipotriene with calcium might increase the risk for hypercalcemia.
Calcipotriene is a vitamin D analog used topically for psoriasis. It can be absorbed in sufficient amounts to cause systemic effects, including hypercalcemia. Theoretically, combining calcipotriene with calcium supplements might increase the risk of hypercalcemia.
Digoxin (Lanoxin)
Using intravenous calcium with digoxin might increase the risk of fatal cardiac arrhythmias.
Hypercalcemia increases the risk of fatal cardiac arrhythmias with digoxin. However, one retrospective analysis of clinical data suggests that intravenous calcium does not increase the risk of dysrhythmias or mortality in patients receiving digoxin.
Diltiazem (Cardizem, Others)
Theoretically, calcium may reduce the therapeutic effects of diltiazem.
Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically, calcium might increase this risk of hypercalcemia and reduce the effectiveness of diltiazem.
Levothyroxine (Synthroid, Others)
Calcium seems to reduce the absorption and effectiveness of levothyroxine.
Advise patients to take levothyroxine and calcium supplements at least 4 hours apart. Calcium reduces levothyroxine absorption, probably by forming insoluble complexes. Calcium carbonate supplements reduce effectiveness of levothyroxine in patients with hypothyroidism.
Lithium
Theoretically, concomitant use of calcium and lithium may increase this risk of hypercalcemia.
Clinical research suggests that long-term use of lithium may cause hypercalcemia in 10% to 60% of patients. Theoretically, concomitant use of lithium and calcium supplements may further increase this risk.
Quinolone Antibiotics
Calcium seems to reduce the absorption of quinolone antibiotics.
Advise patients to take oral quinolones at least 2 hours before or 4-6 hours after calcium supplements or calcium-fortified foods. Taking calcium at the same time as oral quinolones can reduce quinolone absorption. Calcium binds to quinolones in the gut.
Raltegravir (Isentress)
Calcium may reduce levels of raltegravir.
Pharmacokinetic research shows that taking a single dose of calcium carbonate 3000 mg along with raltegravir 400 mg twice daily modestly decreases the mean area under the curve of raltegravir, but the decrease does not necessitate a dose adjustment of raltegravir. However, a case of elevated HIV-1 RNA levels and documented resistance to raltegravir has been reported for a patient taking calcium carbonate 1 gram three times daily plus vitamin D3 (cholecalciferol) 400 IU three times daily in combination with raltegravir 400 mg twice daily for 11 months. It is thought that calcium reduced raltegravir levels by chelation, leading to treatment failure.
Sotalol (Betapace)
Calcium seems to reduce the absorption of sotalol.
Advise patients to separate doses by at least 2 hours before or 4-6 hours after calcium. Calcium appears to reduce the absorption of sotalol, probably by forming insoluble complexes.
Tetracycline Antibiotics
Calcium seems to reduce the absorption of tetracycline antibiotics.
Advise patients to take oral tetracyclines at least 2 hours before, or 4-6 hours after calcium supplements. Taking calcium at the same time as oral tetracyclines can reduce tetracycline absorption. Calcium binds to tetracyclines in the gut.
Thiazide Diuretics
Taking calcium along with thiazides might increase the risk of hypercalcemia and renal failure.
Thiazides reduce calcium excretion by the kidneys. Using thiazides along with moderately large amounts of calcium carbonate increases the risk of milk-alkali syndrome (hypercalcemia, metabolic alkalosis, renal failure). Patients may need to have their serum calcium levels and/or parathyroid function monitored regularly.
Verapamil (Calan, Others)
Theoretically, calcium may reduce the therapeutic effects of verapamil.
Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically, use of calcium supplements may increase this risk of hypercalcemia and reduce the effectiveness of verapamil.
Calcium Channel Blockers
Intravenous calcium may decrease the effects of calcium channel blockers; oral calcium is unlikely to have this effect.
Intravenous calcium is used to decrease the effects of calcium channel blockers in the management of overdose. Intravenous calcium gluconate has been used before intravenous verapamil (Isoptin) to prevent or reduce the hypotensive effects without affecting the antiarrhythmic effects. But there is no evidence that dietary or supplemental calcium when taken orally interacts with calcium channel blockers.
Whey Protein Concentrate
Levodopa
Theoretically, whey protein might decrease levodopa absorption.
Small clinical studies show that concomitant ingestion of protein or high doses of leucine or isoleucine (100 mg/kg) and levodopa can exacerbate tremor, rigidity, and the "on-off" syndrome in patients with Parkinson disease.
Bisphosphonates
Theoretically, whey protein might reduce the absorption of bisphosphonates.
Whey protein contains minerals such as calcium that bind bisphosphonates in the gut. Advise patients to take bisphosphonates at least 30 minutes before whey protein, but preferably at a different time of day.
Quinolone Antibiotics
Theoretically, whey protein might decrease quinolone absorption.
Whey protein contains minerals, such as calcium, that can bind to quinolones in the gut. To avoid this interaction, advise patients to take oral quinolones at least 2 hours before or 4-6 hours after whey protein.
Tetracycline Antibiotics
Theoretically, whey protein might decrease tetracycline absorption.
Whey protein contains minerals, such as calcium, that bind to tetracyclines in the gut. To avoid this interaction, advise patients to take oral tetracyclines at least 2 hours before or 4-6 hours after whey protein.
L-Glutamine
Anticonvulsants
Theoretically, glutamine might antagonize the effects of anticonvulsant medications.
Glutamine is metabolized to the excitatory neurotransmitter glutamate. Glutamate might have antagonistic effects with anticonvulsant drugs. However, this interaction has not yet been reported in humans.
Brand information
Manufacturer and brand details for Whey Sport Vanilla, from the product label.
Whey Sport Vanilla by Cellucor: Common Questions
Does Whey Sport Vanilla by Cellucor interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Will this help me build muscle if I work out regularly?
What side effects does whey protein commonly cause?
Is it safe to take this while pregnant or breastfeeding?
How much sodium does this powder contain?
Can I take this if I have kidney disease?
Does this product have a lot of fillers?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Whey Sport Vanilla is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Whey Sport Vanilla’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Glutamine
Interacts with 50 drugsGlutamine is the most abundant amino acid in the body and is usually made in your muscles. A prescription form is FDA-approved to help reduce sickle cell disease complications, but for most...
Read the full Glutamine monograph → Herb & supplement monographSodium
Interacts with 205 drugsSodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets get more than enough—often too much—from...
Read the full Sodium monograph → Herb & supplement monographVitamin C
Interacts with 207 drugsVitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for immune function, collagen, and acts as an...
Read the full Vitamin C monograph → Herb & supplement monographCalcium
Interacts with 168 drugsCalcium is an essential mineral your body needs for strong bones, nerve signaling, and muscle function, and supplements can help fill gaps when diet falls short. Most people do best getting...
Read the full Calcium monograph → Herb & supplement monographWhey Protein
Interacts with 53 drugsWhey protein is a high-quality, complete protein made from cow's milk that can help people meet protein needs and support muscle growth when combined with exercise. It is generally safe for...
Read the full Whey Protein monograph → Herb & supplement monographCreatine
Creatine is one of the most studied sports supplements, with solid evidence that it can boost strength and performance during short, high-intensity activities like weightlifting and sprintin...
Read the full Creatine monograph →Sources & How We Checked
Whey Sport Vanilla's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 273 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Glutamine 11 references
- Miller AL. Therapeutic considerations of L-glutamine: a review of the literature. Altern Med Rev 1999;4:239-48..
- Bozzetti F, Biganzoli L, Gavazzi C, et al. Glutamine supplementation in cancer patients receiving chemotherapy: a double-blind randomized study. Nutrition 1997;13:748-51.. PubMed
- Mebane AH. L-Glutamine and mania. Am J Psychiatry 984;141:1302-3.
- Meldrum BS. Glutamate as a neurotransmitter in the brain: review of physiology and pathology. J Nutr 2000;130:1007S-15S.. PubMed
- Garlick PJ. Assessment of the safety of glutamine and other amino acids. J Nutr 2001;131:2556S-61S.. PubMed
- Chapman AG. Glutamate and epilepsy. J Nutr 2000;130:1043S-5S.. PubMed
- Ziegler TR. Glutamine supplementation in cancer patients receiving bone marrow transplantation and high dose chemotherapy. J Nutr 2001;131:2578S-84S.. PubMed
- Laviano A, Molfino A, Lacaria MT, Canelli A, De Leo S, Preziosa I, Rossi Fanelli F. Glutamine supplementation favors weight loss in nondieting obese female patients. A pilot study. Eur J Clin Nutr. 2014 Nov;68(11):1264-6. PubMed
- Endari (l-glutamine) [package insert]. Torrance, CA: Emmaus Medical,Inc; 2017.
- Niihara Y, Miller ST, Kanter J, et al. A Phase 3 Trial of l-Glutamine in Sickle Cell Disease. N Engl J Med 2018;379(3):226-35. doi: 10.1056/NEJMoa1715971.
- Ogden HB, Child RB, Fallowfield JL, et al. Gastrointestinal Tolerance of Low, Medium and High Dose Acute Oral l-Glutamine Supplementation in Healthy Adults: A Pilot Study. Nutrients. 2020;12(10):2953. PubMed
Sodium 38 references
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Food and Drug Administration Science Background: Safety of Sodium Phosphates Oral Solution. September 17, 2001. Available at: http://www.fda.gov/cder/drug/safety/sodiumphospate.htm
- Coton T, Mallaret C, Coilliot C, Carre D, Guisset M. Severe acute ulcerated gastritis induced by salt. Presse Med 2009;38(3):499-500. PubMed
- Frings-Meuthen P, Buehlmeier J, Baecker N, et al. High sodium chloride intake exacerbates immobilization-induced bone resorption and protein losses. J Appl Physiol 2011;111(2):537-542. PubMed
- Frings-Meuthen P, Baecker N, Heer M. Low-grade metabolic acidosis may be the cause of sodium chloride-induced exaggerated bone resorption. J Bone Miner Res 2008;23(4):517-524. PubMed
- Alam S, Johnson AG. A meta-analysis of randomised controlled trials (RCT) among healthy normotensive and essential hypertensive elderly patients to determine the effect of high salt (NaCl) diet of blood pressure. J Hum Hypertens 1999;13(6):367-74.
- Boudville N, Ward S, Benaroia M, House AA. Increased sodium intake correlates with greater use of antihypertensive agents by subjects with chronic kidney disease. Am J Hypertens 2005;18(10):1300-5. PubMed
- Bennett WM. Drug interactions and consequences of sodium restriction. Am J Clin Nutr 1997;65(2 Suppl):678S-681S. PubMed
- Okusa MD, Crystal LJ. Clinical manifestations and management of acute lithium intoxication. Am J Med 1994;97(4):383-9. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary reference intakes for water, potassium, sodium, chloride, and sulfate. Washington, DC: National Academy Press, 2005. Available at: http://www.nap.edu/openbook.php?record_id=10925. DOI
- D'Elia L, Rossi G, Ippolito R, Cappuccio FP, Strazzullo P. Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clin Nutr 2012;31(4):489-98. PubMed
- Goldsmith SR. Hyponatremia in heart failure: time for a trial. J Card Fail 2013;19(6):398-400. PubMed
- Willocks L, Brettle R, Keen J, Valentine C, Pinching AJ. Formulations of didanosine (ddI) and salt overload. Lancet 1992;339(8786):190.
- Chen L, Zhang Z, Chen W, Whelton PK, Appel LJ. Lower Sodium Intake and Risk of Headaches: Results From the Trial of Nonpharmacologic Interventions in the Elderly. Am J Public Health. 2016;106(7):1270-5. PubMed
- Cook NR, Appel LJ, Whelton PK. Lower levels of sodium intake and reduced cardiovascular risk. Circulation. 2014;129(9):981-9. PubMed
- Cook NR, Appel LJ, Whelton PK. Sodium Intake and All-Cause Mortality Over 20 Years in the Trials of Hypertension Prevention. J Am Coll Cardiol. 2016;68(15):1609-1617. PubMed
- Mente A, O'Donnell M, Rangarajan S, et al. Associations of urinary sodium excretion with cardiovascular events in individuals with and without hypertension: a pooled analysis of data from four studies. Lancet. 2016;388(10043):465-75. PubMed
- Moosavian SP, Haghighatdoost F, Surkan PJ, Azadbakht L. Salt and obesity: a systematic review and meta-analysis of observational studies. Int J Food Sci Nutr. 2017;68(3):265-277. PubMed
- O'Donnell M, Mente A, Rangarajan S, et al. Urinary sodium and potassium excretion, mortality, and cardiovascular events. N Engl J Med. 2014;371(7):612-23. DOI
- Poggio R, Gutierrez L, Matta MG, Elorriaga N, Irazola V, Rubinstein A. Daily sodium consumption and CVD mortality in the general population: systematic review and meta-analysis of prospective studies. Public Health Nutr. 2015;18(4):695-704. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Mahtani KR, Heneghan C, Onakpoya I, et al. Reduced Salt Intake for Heart Failure: A Systematic Review. JAMA Intern Med. 2018 Dec 1;178(12):1693-1700. PubMed
- Yancy CW. Sodium Restriction in Heart Failure: Too Much Uncertainty-Do the Trials. JAMA Intern Med. 2018 Dec 1;178(12):1700-1701. PubMed
- He FJ, Campbell NRC, Ma Y, MacGregor GA, Cogswell ME, Cook NR. Errors in estimating usual sodium intake by the Kawasaki formula alter its relationship with mortality: implications for public health. Int J Epidemiol. 2018;47(6):1784-1795. PubMed
- Murthy K, Ondrey GJ, Malkani N, et al. THE EFFECTS OF HYPONATREMIA ON BONE DENSITY AND FRACTURES: A SYSTEMATIC REVIEW AND META-ANALYSIS. Endocr Pract. 2019;25(4):366-378. PubMed
- Messerli FH, Hofstetter L, Syrogiannouli L, et al. Sodium intake, life expectancy, and all-cause mortality. Eur Heart J 2021;42(21):2103-2112. PubMed
- Graudal NA, Hubeck-Graudal T, Jurgens G. Effects of low sodium diet versus high sodium diet on blood pressure, renin, aldosterone, catecholamines, cholesterol, and triglyceride. Cochrane Database Syst Rev 2020;12(12):CD004022. PubMed
- Giatti S, Santos RB, Aielo AN, et al. Association of sodium with obstructive sleep apnea. The ELSA-Brasil study. Ann Am Thorac Soc 2021;18(3):502-510. PubMed
- Nan X, Lu H, Wu J, et al. The interactive association between sodium intake, alcohol consumption and hypertension among elderly in northern China: a cross-sectional study. BMC Geriatr 2021;21(1):135. PubMed
- Kyozuka H, Fukusda T, Murata T, et al. Impact of preconception sodium intake on hypertensive disorders of pregnancy: The Japan Environment and Children's study. Pregnancy Hypertens 2021;23:66-72. PubMed
- Zhao L, Ogden CL, Yang Q, et al. Association of usual sodium intake with obesity among US children and adolescents, NHANES 2009-2016. Obesity (Silver Spring) 2021;29(3):587-594. PubMed
- Ma Y, He FJ, Sun Q, et al. 24-Hour urinary sodium and potassium excretion and cardiovascular risk. N Engl J Med 2022;386(3):252-263. PubMed
- Liu J, Yang X, Zhang P, et al. Association of urinary sodium excretion and left ventricular hypertrophy in people with type 2 diabetes mellitus: A cross-sectional study. Front Endocrinol (Lausanne) 2021;12:728493. PubMed
- Filippini T, Malavolti M, Whelton PK, Vinceti M. Sodium intake and risk of hypertension: A systematic review and dose-response meta-analysis of observational cohort studies. Curr Hypertens Rep 2022;24(5):133-144. PubMed
- Wang DD, Li Y, Nguyen XT, et al. Dietary sodium and potassium intake and risk of non-fatal cardiovascular diseases: The million veteran program. Nutrients 2022;14(5):1121. PubMed
- Kwak JH, Park CH, Eun CS, et al. The associations of dietary intake of high sodium and low zinc with gastric cancer mortality: A prospective cohort study in Korea. Nutr Cancer 2022;74(10):3501-3508. PubMed
- George S, Maiti R, Mishra BR, Jena M, Mohapatra D. Effect of regulated add-on sodium chloride intake on stabilization of serum lithium concentration in bipolar disorder: A randomized controlled trial. Bipolar Disord 2023;25(1):66-75. PubMed
- Zhou TL, Schütten MTJ, Kroon AA, et al. Urinary Sodium Excretion and Salt Intake Are Not Associated With Blood Pressure Variability in a White General Population. J Am Heart Assoc 2023;12(1):e026578. PubMed
Vitamin C 51 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Back DJ, Breckenridge AM, MacIver M, et al. Interaction of ethinyloestradiol with ascorbic acid in man. Br Med J (Clin Res Ed) 1981;282:1516.
- Morris JC, Beeley L, Ballantine N. Interaction of ethinyloestradiol with ascorbic acid in man [letter]. Br Med J (Clin Res Ed) 1981;283:503.
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Dwyer JH, Merz NB, Shirocre AM, et al. Progression of early atherosclerosis and intake of vitamin C and vitamin E from supplements and food. The Los Angeles Atherosclerosis Study. 41st Annual Conference on Cardiovascular Disease Epidemiology and Prevent
- Levine M, Rumsey SC, Daruwala R, et al. Criteria and recommendations for vitamin C intake. JAMA 1999;281:1415-23. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Houston JB, Levy G. Drug biotransformation interactions in man VI: Acetaminophen and ascorbic acid. J Pharm Sci 1976;65:1218-21. PubMed
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Rosenthal G. Interaction of ascorbic acid and warfarin. JAMA 1971;215:1671. DOI
- Hume R, Johnstone JM, Weyers E. Interaction of ascorbic acid and warfarin. JAMA 1972;219:1479. DOI
- Smith EC, Skalski RJ, Johnson GC, Rossi GV. Interaction of ascorbic acid and warfarin. JAMA 1972;221:1166. DOI
- Traxer O, Huet B, Poindexter J, et al. Effect of ascorbic acid consumption on urinary stone risk factors. J Urol 2003;170:397-401.. PubMed
- Domingo JL, Gomez M, Llobet JM, Richart C. Effect of ascorbic acid on gastrointestinal aluminum absorption (letter). Lancet 1991;338:1467.
- Domingo JL, Gomez M, Llobet JM, Corbella J. Influence of some dietary constituents on aluminum absorption and retention in rats. Kidney Int 1991;39:598-601. PubMed
- Partridge NA, Regnier FE, White JL, Hem SL. Influence of dietary constituents on intestinal absorption of aluminum. Kidney Int 1989;35:1413-7. PubMed
- Mc Leod DC, Nahata MC. Inefficacy of ascorbic acid as a urinary acidifier (letter). N Engl J Med 1977;296:1413. DOI
- Hansten PD, Hayton WL. Effect of antacid and ascorbic acid on serum salicylate concentration. J Clin Pharmacol 1980;20:326-31. PubMed
- Dysken MW, Cumming RJ, Channon RA, Davis JM. Drug interaction between ascorbic acid and fluphenazine. JAMA 1979;241:2008. DOI
- Vihtamaki T, Parantainen J, Koivisto AM, et al. Oral ascorbic acid increases plasma oestradiol during postmenopausal hormone replacement therapy. Maturitas 2002;42:129-35. PubMed
- Slain D, Amsden JR, Khakoo RA, et al. Effect of high-dose vitamin C on the steady-state pharmacokinetics of the protease inhibitor indinavir in healthy volunteers. Pharmacotherapy 2005;25:165-70. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Feetam CL, Leach RH, Meynell MJ. Lack of a clinically important interaction between warfarin and ascorbic acid. Toxicol Appl Pharmacol 1975;31:544-7. PubMed
- Weintraub M, Griner PF. Warfarin and ascorbic acid: lack of evidence for a drug interaction. Toxicol Appl Pharmacol 1974;28:53-6. PubMed
- Lee DH, Folsom AR, Harnack L, et al. Does supplemental vitamin C increase cardiovascular disease risk in women with diabetes? Am J Clin Nutr 2004;80:1194-200. PubMed
- Taylor EN, Stampfer MJ, Curhan GC. Dietary factors and the risk of incident kidney stones in men: new insights after 14 years of follow-up. J Am Soc Nephrol 2004;15:3225-32. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Fairweather-Tait S, Hickson K, McGaw B, et al. Orange juice enhances aluminium absorption from antacid preparation. Eur J Clin Nutr. 1994;48(1):71-3.
- Gruenwald, J., Graubaum, H. J., Busch, R., and Bentley, C. Safety and tolerance of ester-C compared with regular ascorbic acid. Adv.Ther. 2006;23(1):171-178.
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Einerson, B., Nathorn, C., Kitiyakara, C., Sirada, M., and Thamlikitkul, V. The efficacy of ascorbic acid in suboptimal responsive anemic hemodialysis patients receiving erythropoietin: a meta-analysis. J Med.Assoc.Thai. 2011;94 Suppl 1:S134-S146.
- Li, G., Li, L., Yu, C., and Chen, L. Effect of vitamins C and E supplementation on Helicobacter pylori eradication: a meta-analysis. Br.J Nutr 2011;106(11):1632-1637.
- Chen X, Shen L, Gu X, et al. High-dose supplementation with vitamin C--induced pediatric urolithiasis: the first case report in a child and literature review. Urology. 2014;84(4):922-4. PubMed
- Sattar A, Willman JE, Kolluri R. Possible warfarin resistance due to interaction with ascorbic acid: case report and literature review. Am J Health Syst Pharm. 2013;70(9):782-6. PubMed
- Yaich S, Chaabouni Y, Charfeddine K, et al. Secondary oxalosis due to excess vitamin C intake: a cause of graft loss in a renal transplant recipient. Saudi J Kidney Dis Transpl. 2014;25(1):113-6. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Rumbold A, Ota E, Nagata C, Shahrook S, Crowther CA. Vitamin C supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004072. PubMed
- Seo MS, Kim JK, Shim JY. High-dose vitamin C promotes regression of multiple pulmonary metastases originating from hepatocellular carcinoma. Yonsei Med J. 2015;56(5):1449-52. PubMed
- Skelin M, Lucijanic T, Amidzic Klaric D, et al. Factors Affecting Gastrointestinal Absorption of Levothyroxine: A Review. Clin Ther. 2017 Feb;39(2):378-403. PubMed
- Jiang K, Tang K, Liu H, Xu H, Ye Z, Chen Z. Ascorbic acid supplements and kidney stones incidence among men and women: a systematic review and meta-analysis. Urol J. 2019;16(2):115-120.
- Thomas S, Patel D, Bittel B, et al. Effect of High-Dose Zinc and Ascorbic Acid Supplementation vs Usual Care on Symptom Length and Reduction Among Ambulatory Patients With SARS-CoV-2 Infection: The COVID A to Z Randomized Clinical Trial. JAMA Netw Open. 2 PubMed
- Giffen MA, McLemore JL. Hyperoxalosis Secondary to Intravenous Vitamin C Administration as a Non-Allopathic Treatment for Cancer. Acad Forensic Pathol 2019;9(1-2):118-126. PubMed
- Maike A, Sturgill D, Gallan A. Oxalate Nephropathy in a Renal Transplant Recipient After Receiving High Dose Ascorbic Acid. Am J Med Sci 2021. PubMed
- Shen ZY, Chen YR, Wang MC, Chang SS. High-dose vitamin C-induced acute oxalate nephropathy in a renal transplant recipient: a case report and literature review. Asian J Surg 2022. PubMed
- Yanase F, Spano S, Maeda A, et al. Mega-dose sodium ascorbate: a pilot, single-dose, physiological effect, double-blind, randomized, controlled trial. Crit Care 2023;27(1):371. PubMed
- Sharma Y, Sumanadasa S, Shahi R, et al. Efficacy and safety of vitamin C supplementation in the treatment of community-acquired pneumonia: a systematic review and meta-analysis with trial sequential analysis. Sci Rep 2024;14(1):11846. PubMed
- Pejcic AV, Petrovic NZ, Djordjic MD, Milosavljevic MN. Vitamin C Levels in Pregnant Women and the Efficacy of Vitamin C Supplements in Preventing Premature Rupture of Membranes: A Systematic Review and Meta-Analysis. Balkan Med J 2024;41(4):248-260. PubMed
Calcium 62 references
- Shils M, Olson A, Shike M. Modern Nutrition in Health and Disease. 8th ed. Philadelphia, PA: Lea and Febiger, 1994.
- Hernandez-Avila M, Gonzalez-Cossio T, Hernandez-Avila JE, et al. Dietary calcium supplements to lower blood lead levels in lactating women: a randomized placebo-controlled trial. Epidemiology 2003;14:206-12.. PubMed
- Thys-Jacobs S, Ceccarelli S, Bierman A, et al. Calcium supplementation in premenstrual syndrome: a randomized crossover trial. J Gen Intern Med 1989;4:183-9. PubMed
- Maton PN, Burton ME. Antacids revisited: a review of their clinical pharmacology and recommended therapeutic use. Drugs 1999;57:855-70.
- Clemens JD, Feinstein AR. Calcium carbonate and constipation: a historical review of medical mythopoeia. Gastroenterology 1977;72:957-61. DOI
- Saunders D, Sillery J, Chapman R. Effect of calcium carbonate and aluminum hydroxide on human intestinal function. Dig Dis Sci 1988;33:409-13. PubMed
- Friedman PA, Bushinsky DA. Diuretic effects on calcium metabolism. Semin Nephrol 1999;19:551-6.
- Koo WK, Walters JC, Esterlitz J, et al. Maternal calcium supplementation and fetal bone mineralization. Obstet Gynecol 1999;94:577-82. DOI
- Raman L, Rajalakshmi K, Krishnamachari KAVR, et al. Effect of calcium supplementation to undernourished mothers during pregnancy on the bone density of the neonates. Am J Clin Nutr 1978; 31:466-9. DOI
- Murry JJ, Healy MD. Drug-mineral interactions: a new responsibility for the hospital dietician. J Am Diet Assoc 1991;91:66-73.
- Chan JM, Giovannucci E, Andersson SO, et al. Dairy products, calcium, phosphorous, vitamin D, and risk of prostate cancer. Cancer Causes Control 1998;9:559-66.
- Butner LE, Fulco PP, Feldman G, et al. Calcium carbonate-induced hypothyroidism. Ann Intern Med 2000:132:595. PubMed
- Schneyer CR. Calcium carbonate and reduction of levothyroxine efficacy. JAMA 1998;279:750. PubMed
- Moser LR, Smythe MA, Tisdale JE. The use of calcium salts in the prevention and management of verapamil-induced hypotension. Ann Pharmacother 2000;34:622-9. PubMed
- Singh N, Singh PN, Hershman JM. Effect of calcium carbonate on the absorption of levothyroxine. JAMA 2000;283:2822-5. PubMed
- Kahela P, Anttila M, Tikkanen R, Sundquist H. Effect of food, food constituents and fluid volume on the bioavailability of sotalol. Acta Pharmacol Toxicol (Copenh) 1979;44:7-12.. PubMed
- Pletz MW, Petzold P, Allen A, et al. Effect of calcium carbonate on bioavailability of orally administered gemifloxacin. Antimicrob Agents Chemother 2003;47:2158-60.. PubMed
- Bar-Or D, Yoel G. Calcium and calciferol antagonize effect of verapamil in atrial fibrillation. Br Med J 1981;282:1585-6.
- Decktor DL, Robinson M, Maton PN, et al. Effects of aluminum/magnesium hydroxide and calcium carbonate on esophageal and gastric pH in subjects with heartburn. Am J Ther 1995;2:546-52. PubMed
- Simoneau G. Absence of rebound effect with calcium carbonate. Eur J Drug Metab Pharmacokinet 1996;21:351-7. PubMed
- Peters ML, Leonard M, Licata AA. Role of alendronate and risedronate in preventing and treating osteoporosis. Cleve Clin J Med 2001;68:945-51. PubMed
- Bourke JF, Mumford R, Whittaker P, et al. The effects of topical calcipotriol on systemic calcium homeostasis in patients with chronic plaque psoriasis. J Am Acad Dermatol 1997;37:929-34.
- Gueguen L, Pointillart A. The bioavailability of dietary calcium. J Am Coll Nutr 2000;19:119s-136s. PubMed
- Vella A, Gerber TC, Hayes DL, Reeder GS. Digoxin, hypercalcaemia, and cardiac conduction. Postgrad Med J 1999;75:554-6. PubMed
- Bania TC, Blaufeux B, Hughes S, et al. Calcium and digoxin vs. calcium alone for severe verapamil toxicity. Acad Emerg Med 2000;7:1089-96. PubMed
- Tseng M, Breslow RA, Graubard BI, Ziegler RG. Dairy, calcium, and vitamin D intakes and prostate cancer risk in the National Health and Nutrition Examination Epidemiologic Follow-up Study cohort. Am J Clin Nutr 2005;81:1147-54. PubMed
- Weingarten MA, Zalmanovici A, Yaphe J. Dietary calcium supplementation for preventing colorectal cancer and adenomatous polyps. Cochrane Database Syst Rev 2004;(1):CD003548. PubMed
- Tavani A, Bertuccio P, Bosetti C, et al. Dietary intake of calcium, vitamin D, phosphorus and the risk of prostate cancer. Eur Urol 2005;48:27-33. PubMed
- Giovannucci E, Liu Y, Stampfer MJ, Willett WC. A prospective study of calcium intake and incident and fatal prostate cancer. Cancer Epidemiol Biomarkers Prev 2006;15:203-10. PubMed
- Rocephin (ceftriaxone) and calcium interaction. Pharmacist's Letter / Prescriber's Letter 2007;23(10):231005.
- Bolland MJ, Barber PA, Doughty RN, et al. Vascular events in healthy older women receiving calcium supplementation: randomised control trial. BMJ 2008;336:262-6.
- Bolland MJ, Avenell A, Baron JA, et al. Effect of calcium supplements on risk of myocardial infarction and cardiovascular events: meta-analysis. BMJ 2010;341:c3691. PubMed
- Calcium supplementation and vascular events. Pharmacist's Letter / Prescriber's Letter 2008;24(3):240306.
- Dietary reference intakes for calcium and vitamin D. Institute of Medicine, November 30, 2010. Available at: http://www.iom.edu/~/media/Files/Report%20Files/2010/Dietary-Reference-Intakes-for-Calcium-and-Vitamin-D/Vitamin%20D%20and%20Calcium%202010%20Repo
- Coburn JW, Mischel MG, Goodman WG, et al. Calcium citrate markedly enhances aluminum absorption from aluminum hydroxide. Am J Kidney Dis. 1991;17(6):708-11. PubMed
- Bradley JS, Wassel RT, Lee L, et al. Intravenous ceftriaxone and calcium in the neonate: assessing the risk for cardiopulmonary adverse events. Pediatrics. 2009;123(4):e609-13. PubMed
- Kays MB, Overholser BR, Mueller BA, et al. Effects of sevelamer hydrochloride and calcium acetate on the oral bioavailability of ciprofloxacin. Am J Kidney Dis. 2003;42(6):1253-9. PubMed
- Neuhofel, A. L., Wilton, J. H., Victory, J. M., Hejmanowsk, L. G., and Amsden, G. W. Lack of bioequivalence of ciprofloxacin when administered with calcium-fortified orange juice: a new twist on an old interaction. J Clin Pharmacol. 2002;42(4):461-466. DOI
- Dickinson, H. O., Nicolson, D. J., Cook, J. V., Campbell, F., Beyer, F. R., Ford, G. A., and Mason, J. Calcium supplementation for the management of primary hypertension in adults. Cochrane.Database.Syst.Rev. 2006;(2):CD004639. PubMed
- Jones, B. J. and Twomey, P. J. Requesting patterns for serum calcium concentration in patients on long-term lithium therapy. Int J Clin Pract. 2009;63(1):170-172. PubMed
- Levine, M., Nikkanen, H., and Pallin, D. J. The effects of intravenous calcium in patients with digoxin toxicity. J Emerg.Med. 2011;40(1):41-46. PubMed
- Castelo-Branco, C., Ciria-Recasens, M., Cancelo-Hidalgo, M. J., Palacios, S., Haya-Palazuelos, J., Carbonell-Abello, J., Blanch-Rubio, J., Martinez-Zapata, M. J., Manasanch, J., and Perez-Edo, L. Efficacy of ossein-hydroxyapatite complex compared with ca
- Li K, Kaaks R, Linseisen J, Rohrmann S. Associations of dietary calcium intake and calcium supplementation with myocardial infarction and stroke risk and overall cardiovascular mortality in the Heidelberg cohort of the European Prospective Investigation i
- Chung M, Tang AM, Fu Z. Calcium Intake and Cardiovascular Disease Risk: An Updated Systematic Review and Meta-analysis. Ann Intern Med. 2016 Oct 25. PubMed
- Nolan CR, Califano JR, Butzin CA. Influence of calcium acetate or calcium citrate on intestinal aluminum absorption. Kidney Int. 1990;38(5):937-41. PubMed
- Lewis JR, Radavelli-Bagatini S, Rejnmark L, et al. The effects of calcium supplementation on verified coronary heart disease hospitalization and death in postmenopausal women: a collaborative meta-analysis of randomized controlled trials. J Bone Miner Res PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Lappe J, Watson P, Travers-Gustafson D, Recker R, Garland C, Gorham E, Baggerly K, McDonnell SL. Effect of Vitamin D and Calcium Supplementation on Cancer Incidence in Older Women: A Randomized Clinical Trial. JAMA. 2017 Mar 28;317(12):1234-1243. PubMed
- Grove ML, Cook D. Calcium and heart attacks. Doesn't apply to most calcium prescriptions. BMJ. 2010;341:c5003. PubMed
- Insentress [package insert]. Whitehouse Station, NJ: Merck Sharp & Dohme Corp.; 2014.
- Roberts JL, Kiser JJ, Hindman JT, Meditz AL. Virologic failure with a raltegravir-containing antiretroviral regimen and concomitant calcium administration. Pharmacotherapy 2011;31(10):298e-302e. DOI
- Vitekta [package insert]. Foster City, CA: Gilead Sciences, Inc.; 2014.
- Storan ER, O'Gorman SM, Murphy A, Laing M. Case Report of Calciphylaxis Secondary to Calcium and Vitamin D<sub>3</sub> Supplementation. J Cutan Med Surg. 2017;21(2):162-163. DOI
- Jenkins DJA, Spence JD, Giovannucci EL, et al. Supplemental vitamins and minerals for CVD prevention and treatment. J Am Coll Cardiol 2018;71(22):2570-84. PubMed
- Borkenhagen JF, Connor EL, Stafstrom CE. Neonatal hypocalcemic seizures due to excessive maternal calcium ingestion. Pediatr Neurol 2013;48(6):469-71. PubMed
- WHO recommendations on antenatal care for a positive pregnancy experience. Geneva: World Health Organization; 2016 (http://www.who.int/reproductivehealth/publications/maternal_perinatal_health/ anc-positive-pregnancy-experience/en/).
- Aune D, Navarro Rosenblatt DA, Chan DS, et al. Dairy products, calcium, and prostate cancer risk: a systematic review and meta-analysis of cohort studies. Am J Clin Nutr. 2015;101(1):87-117. PubMed
- Lan T, Park Y, Colditz GA, et al. Adolescent dairy product and calcium intake in relation to later prostate cancer risk and mortality in the NIH-AARP Diet and Health Study. Cancer Causes Control. 2020;31(10):891-904. PubMed
- Zhang Y, Li Y, Liu J, et al. Association of Vitamin D or Calcium Supplementation with Cardiovascular Outcomes and Mortality: A Meta-Analysis with Trial Sequential Analysis. J Nutr Health Aging 2021;25(2):263-270. PubMed
- Myung SK, Kim HB, Lee YJ, Choi YJ, Oh SW. Calcium Supplements and Risk of Cardiovascular Disease: A Meta-Analysis of Clinical Trials. Nutrients 2021;13(2):368. PubMed
- Hetaimish B. Neonatal Calcinosis Cutis After Treatment of Hypocalcemia with Calcium Gluconate: A Report of 2 Cases. Am J Case Rep 2024;25:e943397. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Whey Protein 25 references
- Martindale W. Martindale the Extra Pharmacopoeia. Pharmaceutical Press, 1999.
- Maton PN, Burton ME. Antacids revisited: a review of their clinical pharmacology and recommended therapeutic use. Drugs 1999;57:855-70.
- Bell SJ. Whey protein concentrates with and without immunoglobulins: a review. J Med Food 2000;3:1-13. PubMed
- Nutt JG, Woodward WR, Hammerstad JP, et al. The "on-off" phenomenon in Parkinson's disease. Relation to levodopa absorption and transport. N Engl J Med 1984;310:483-8. PubMed
- Baruzzi A, Contin M, Riva R, et al. Influence of meal ingestion time on pharmacokinetics of orally administered levodopa in parkinsonian patients. Clin Neuropharmacol 1987;10:527-37. PubMed
- Juncos JL, Fabbrini G, Mouradian MM, et al. Dietary influences on the antiparkinsonian response to levodopa. Arch Neurol 1987;44:1003-5. PubMed
- Eriksson T, Granerus AK, Linde A, et al. "On-off" phenomenon in Parkinson's disease: relationship between dopa and other large neutral amino acids in plasma. Neurology 1988;38:1245-8. PubMed
- Semla TP, Beizer JL, Higbee MD. Geriatric Dosage Handbook. 4th ed. Hudson, OH: Lexicomp, 1998.
- Pletz MW, Petzold P, Allen A, et al. Effect of calcium carbonate on bioavailability of orally administered gemifloxacin. Antimicrob Agents Chemother 2003;47:2158-60.. PubMed
- Peters ML, Leonard M, Licata AA. Role of alendronate and risedronate in preventing and treating osteoporosis. Cleve Clin J Med 2001;68:945-51. PubMed
- Micke, P., Beeh, K. M., and Buhl, R. Effects of long-term supplementation with whey proteins on plasma glutathione levels of HIV-infected patients. Eur.J Nutr 2002;41(1):12-18. PubMed
- Chitapanarux, T., Tienboon, P., Pojchamarnwiputh, S., and Leelarungrayub, D. Open-labeled pilot study of cysteine-rich whey protein isolate supplementation for nonalcoholic steatohepatitis patients. J Gastroenterol.Hepatol. 2009;24(6):1045-1050. PubMed
- Sataloff, R. T., Bittermann, T., Marks, L., Lurie, D., and Hawkshaw, M. The effects of glutathione enhancement on sensorineural hearing loss. Ear Nose Throat J 2010;89(9):422-433.
- Zhu, K., Meng, X., Kerr, D. A., Devine, A., Solah, V., Binns, C. W., and Prince, R. L. The effects of a two-year randomized, controlled trial of whey protein supplementation on bone structure, IGF-1, and urinary calcium excretion in older postmenopausal
- Bjorkman, M. P., Pilvi, T. K., Kekkonen, R. A., Korpela, R., and Tilvis, R. S. Similar effects of leucine rich and regular dairy products on muscle mass and functions of older polymyalgia rheumatica patients: a randomized crossover trial. J Nutr Health A
- Brun, A. C., Stordal, K., Johannesdottir, G. B., Bentsen, B. S., and Medhus, A. W. The effect of protein composition in liquid meals on gastric emptying rate in children with cerebral palsy. Clin.Nutr 2012;31(1):108-112. PubMed
- Gouni-Berthold, I., Schulte, D. M., Krone, W., Lapointe, J. F., Lemieux, P., Predel, H. G., and Berthold, H. K. The whey fermentation product malleable protein matrix decreases TAG concentrations in patients with the metabolic syndrome: a randomised plac
- Errichiello, L., Pezzella, M., Santulli, L., Striano, S., Zara, F., Minetti, C., Mainardi, P., and Striano, P. A proof-of-concept trial of the whey protein alfa-lactalbumin in chronic cortical myoclonus. Mov Disord. 2011;26(14):2573-2575. PubMed
- Carcillo, J. A., Dean, J. M., Holubkov, R., Berger, J., Meert, K. L., Anand, K. J., Zimmerman, J., Newth, C. J., Harrison, R., Burr, J., Willson, D. F., and Nicholson, C. The randomized comparative pediatric critical illness stress-induced immune suppres
- Chungchunlam, S. M., Moughan, P. J., Henare, S. J., and Ganesh, S. Effect of time of consumption of preloads on measures of satiety in healthy normal weight women. Appetite 2012;59(2):281-288. PubMed
- Rencuzogullari I, Börekçi A, Karakoyun S, et al. Coronary thrombosis in three coronary arteries due to whey protein. Am J Emerg Med. 2017;35(4):664.e3-664.e4. PubMed
- Silverberg NB. Whey protein precipitating moderate to severe acne flares in 5 teenaged athletes. Case Reports Cutis. 2012;90(2):70-2.
- Simonart T. Acne and whey protein supplementation among bodybuilders. Dermatology. 2012;225(3):256-8. PubMed
- Pontes TC, Costa Fernandes Filho GM, Pereira Trindade AS, Sobral Filho JF. Incidence of acne vulgaris in young adult users of protein-calorie supplements in the city of João Pessoa-PB. An Bras Dermatol. 2013;88(6):907-12.
- Adebamowo CA, Spiegelman D, Berkey CS, et al. Milk consumption and acne in teenaged boys. J Am Acad Dermatol. 2008 May;58(5):787-93. PubMed
Creatine 86 references
- Koshy KM, Griswold E, Schneeberger EE. Interstitial nephritis in a patient taking creatine. N Engl J Med 1999;340:814-5. PubMed
- Vahedi K, Domingo V, Amarenco P, Bousser MG. Ischemic stroke in a sportsman who consumed MaHuang extract and creatine monohydrate for bodybuilding. J Neurol Neurosurg Psychiatr 2000;68:112-3.
- Greenhaff P. Renal dysfunction accompanying oral creatine supplements. Lancet 1998;352:233-4. PubMed
- Vandenberghe K, Goris M, Van Hecke P, et al. Long-term creatine intake is beneficial to muscle performance during resistance training (abstract). J Appl Physiol 1997;83:2055-63. PubMed
- Hultman E, Soderlund K, Timmons JA, et al. Muscle creatine loading in men. J Appl Physiol 1996;81:232-7. PubMed
- Pritchard NR, Kalra PA. Renal dysfunction accompanying oral creatine supplements. Lancet 1998;351:1252-3. PubMed
- Poortmans JR, Auquier H, Renaut V, et al. Effect of short-term creatine supplementation on renal responses in men (abstract). Eur J Appl Physiol Occup Physiol 1997;76:566-7. PubMed
- Poortmans JR, Francaux M. Long-term oral creatine supplementation does not impair renal function in healthy athletes. Med Sci Sports Exerc 1999;31:1108-10. PubMed
- Mihic S, MacDonald JR, McKenzie S, Tarnopolsky MA. Acute creatine loading increases fat-free mass, but does not affect blood pressure, plasma creatinine, or CK activity in men and women. Med Sci Sports Exerc 2000;32:291-6. PubMed
- Rawson ES, Wehnert ML, Clarkson PM. Effects of 30 days of creatine ingestion in older men. Eur J Appl Physiol Occup Physiol 1999;80:139-44. PubMed
- Earnest CP, Almada AL, Mitchell TL. High-performance capillary electrophoresis-pure creatine monohydrate reduces blood lipids in men and women. Clin Sci (Colch) 1996;91:113-8. PubMed
- Juhn MS. Oral creatine supplementation. Separating fact from hype. Phys Sportsmed 1999;27:47-50,53-54,56,61,89. PubMed
- Juhn MS, O'Kane JW, Vinci DM. Oral creatine supplementation in male collegiate athletes: a survey of dosing habits and side effects. J Am Diet Assoc 1999;99:593-5.
- Green AL, Hultman E, Macdonald IA, et al. Carbohydrate ingestion augments skeletal muscle creatine accumulation during creatine supplementation in humans. Am J Physiol 1996;271:E821-6. PubMed
- Balsom PD, Soderlund K, Sjodin B, Ekblom B. Skeletal muscle metabolism during short duration high-intensity exercise: influence of creatine supplementation. Acta Physiol Scand 1995;154:303-10. PubMed
- Snow RJ, McKenna MJ, Selig SE, et al. Effect of creatine supplementation on sprint exercise performance and muscle metabolism. (abstract) J Appl Physiol 1998;84:1667-73. PubMed
- McNaughton LR, Dalton B, Tarr J. The effects of creatine supplementation on high-intensity exercise performance in elite performers. (abstract) Eur J Appl Physiol Occup Physiol 1998;78:236-40. PubMed
- Groeneveld GJ, Veldink JH, van der Tweel I, et al. A randomized sequential trial of creatine in amyotrophic lateral sclerosis. Ann Neurol 2003;53:437-45. . PubMed
- Robinson SJ. Acute quadriceps compartment syndrome and rhabdomyolysis in a weight lifter using high-dose creatine supplementation. J Am Board Fam Pract 2000;13:134-7. PubMed
- Kammer RT. Lone atrial fibrillation associated with creatine monohydrate supplementation. Pharmacotherapy 2005;25:762-4. PubMed
- Gualano B, Ugrinowitsch C, Novaes RB, et al. Effects of creatine supplementation on renal function: a randomized, double-blind, placebo-controlled clinical trial. Eur J Appl Physiol 2008;103:33-40. PubMed
- Pfeffer, G., Majamaa, K., Turnbull, D. M., Thorburn, D., and Chinnery, P. F. Treatment for mitochondrial disorders. Cochrane Database.Syst.Rev. 2012;4:CD004426. PubMed
- Boos, C. J., White, S. H., Bland, S. A., and McAllister, P. D. Dietary supplements and military operations: caution is advised. J R.Army Med Corps 2010;156(1):41-43. PubMed
- Kreider, R. B. Dietary supplements and the promotion of muscle growth with resistance exercise. Sports Med 1999;27(2):97-110. PubMed
- Juhn, M. S., O'Kane, J. W., and Vinci, D. M. Oral creatine supplementation in male collegiate athletes: a survey of dosing habits and side effects. J Am.Diet.Assoc 1999;99(5):593-595.
- Volek, J. S., Duncan, N. D., Mazzetti, S. A., Putukian, M., Gomez, A. L., and Kraemer, W. J. No effect of heavy resistance training and creatine supplementation on blood lipids. Int J Sport Nutr.Exerc.Metab 2000;10(2):144-156. PubMed
- Robinson, T. M., Sewell, D. A., Casey, A., Steenge, G., and Greenhaff, P. L. Dietary creatine supplementation does not affect some haematological indices, or indices of muscle damage and hepatic and renal function. Br.J Sports Med 2000;34(4):284-288. PubMed
- Tarnopolsky, M. A. Potential benefits of creatine monohydrate supplementation in the elderly. Curr.Opin.Clin Nutr.Metab Care 2000;3(6):497-502. PubMed
- Tarnopolsky, M. A. and MacLennan, D. P. Creatine monohydrate supplementation enhances high-intensity exercise performance in males and females. Int J Sport Nutr.Exerc.Metab 2000;10(4):452-463. PubMed
- Arciero, P. J., Hannibal, N. S., III, Nindl, B. C., Gentile, C. L., Hamed, J., and Vukovich, M. D. Comparison of creatine ingestion and resistance training on energy expenditure and limb blood flow. Metabolism 2001;50(12):1429-1434. PubMed
- Chrusch, M. J., Chilibeck, P. D., Chad, K. E., Davison, K. S., and Burke, D. G. Creatine supplementation combined with resistance training in older men. Med Sci.Sports Exerc. 2001;33(12):2111-2117. PubMed
- Cox, G., Mujika, I., Tumilty, D., and Burke, L. Acute creatine supplementation and performance during a field test simulating match play in elite female soccer players. Int J Sport Nutr.Exerc.Metab 2002;12(1):33-46. PubMed
- Kilduff, L. P., Vidakovic, P., Cooney, G., Twycross-Lewis, R., Amuna, P., Parker, M., Paul, L., and Pitsiladis, Y. P. Effects of creatine on isometric bench-press performance in resistance-trained humans. Med Sci.Sports Exerc. 2002;34(7):1176-1183. PubMed
- Brose, A., Parise, G., and Tarnopolsky, M. A. Creatine supplementation enhances isometric strength and body composition improvements following strength exercise training in older adults. J Gerontol A Biol.Sci.Med Sci. 2003;58(1):11-19. PubMed
- Volek, J. S., Ratamess, N. A., Rubin, M. R., Gomez, A. L., French, D. N., McGuigan, M. M., Scheett, T. P., Sharman, M. J., Hakkinen, K., and Kraemer, W. J. The effects of creatine supplementation on muscular performance and body composition responses to
- Tyler, T. F., Nicholas, S. J., Hershman, E. B., Glace, B. W., Mullaney, M. J., and McHugh, M. P. The effect of creatine supplementation on strength recovery after anterior cruciate ligament (ACL) reconstruction: a randomized, placebo-controlled, double-b DOI
- Groeneveld, G. J., Beijer, C., Veldink, J. H., Kalmijn, S., Wokke, J. H., and van den Berg, L. H. Few adverse effects of long-term creatine supplementation in a placebo-controlled trial. Int J Sports Med 2005;26(4):307-313. PubMed
- Astorino, T. A., Marrocco, A. C., Gross, S. M., Johnson, D. L., Brazil, C. M., Icenhower, M. E., and Kneessi, R. J. Is running performance enhanced with creatine serum ingestion? J Strength.Cond.Res 2005;19(4):730-734. PubMed
- Cramer, J. T., Stout, J. R., Culbertson, J. Y., and Egan, A. D. Effects of creatine supplementation and three days of resistance training on muscle strength, power output, and neuromuscular function. J Strength.Cond.Res 2007;21(3):668-677. PubMed
- Young, P., De, Jonghe P., Stogbauer, F., and Butterfass-Bahloul, T. Treatment for Charcot-Marie-Tooth disease. Cochrane.Database.Syst.Rev. 2008;(1):CD006052. PubMed
- Ostojic, S. M. and Ahmetovic, Z. Gastrointestinal distress after creatine supplementation in athletes: are side effects dose dependent? Res.Sports Med. 2008;16(1):15-22. PubMed
- Whitt, K. N., Ward, S. C., Deniz, K., Liu, L., Odin, J. A., and Qin, L. Cholestatic liver injury associated with whey protein and creatine supplements. Semin.Liver Dis. 2008;28(2):226-231. PubMed
- Koenig CA, Benardot D Cody M Thompson WR. Comparison of creatine monohydrate and carbohydrate supplementation on repeated jump height performance. J Strength Cond Res. 2008;22(4):1081-1086. PubMed
- Gordon, P. H., Cheung, Y. K., Levin, B., Andrews, H., Doorish, C., Macarthur, R. B., Montes, J., Bednarz, K., Florence, J., Rowin, J., Boylan, K., Mozaffar, T., Tandan, R., Mitsumoto, H., Kelvin, E. A., Chapin, J., Bedlack, R., Rivner, M., McCluskey, L.
- Bender, A., Samtleben, W., Elstner, M., and Klopstock, T. Long-term creatine supplementation is safe in aged patients with Parkinson disease. Nutr.Res. 2008;28(3):172-178. PubMed
- Parness, J. You're "hot" from pumping iron? Anesth.Analg. 2009;108(3):711-713. PubMed
- Gualano, B., Ferreira, D. C., Sapienza, M. T., Seguro, A. C., and Lancha, A. H., Jr. Effect of short-term high-dose creatine supplementation on measured GFR in a young man with a single kidney. Am.J.Kidney Dis. 2010;55(3):e7-e9. PubMed
- Saidi, H. and Mani, M. Severe metabolic acidosis secondary to coadministration of creatine and metformin, a case report. Am.J.Emerg.Med. 2010;28(3):388-6. PubMed
- Gualano, B., de, Salles Painelli, V, Roschel, H., Lugaresi, R., Dorea, E., Artioli, G. G., Lima, F. R., da Silva, M. E., Cunha, M. R., Seguro, A. C., Shimizu, M. H., Otaduy, M. C., Sapienza, M. T., da Costa, Leite C., Bonfa, E., and Lancha Junior, A. H.
- Neves, M., Jr., Gualano, B., Roschel, H., Lima, F. R., Lucia, de Sa-Pinto, Seguro, A. C., Shimizu, M. H., Sapienza, M. T., Fuller, R., Lancha, A. H., Jr., and Bonfa, E. Effect of creatine supplementation on measured glomerular filtration rate in postmeno
- Gufford, B. T., Sriraghavan, K., Miller, N. J., Miller, D. W., Gu, X., Vennerstrom, J. L., and Robinson, D. H. Physicochemical characterization of creatine N-methylguanidinium salts. J.Diet.Suppl 2010;7(3):240-252.
- Lugaresi, R., Leme, M., de, Salles Painelli, V, Murai, I. H., Roschel, H., Sapienza, M. T., Lancha Junior, A. H., and Gualano, B. Does long-term creatine supplementation impair kidney function in resistance-trained individuals consuming a high-protein di
- Poortmans, J. R. and Francaux, M. Renal dysfunction accompanying oral creatine supplements. Lancet 7-18-1998;352(9123):234. PubMed
- Maganaris, C. N. and Maughan, R. J. Creatine supplementation enhances maximum voluntary isometric force and endurance capacity in resistance trained men. Acta Physiol Scand. 1998;163(3):279-287. PubMed
- Vandebuerie, F., Vanden Eynde, B., Vandenberghe, K., and Hespel, P. Effect of creatine loading on endurance capacity and sprint power in cyclists. Int J Sports Med 1998;19(7):490-495. PubMed
- Juhn, M. S. and Tarnopolsky, M. Oral creatine supplementation and athletic performance: a critical review. Clin J Sport Med 1998;8(4):286-297. PubMed
- Vandenberghe K, Van Hecke P, Van Leemputte M, and et al. Inhibition of muscle phosphocreatine resynthesis by caffeine after creatine loading. Med Sci Sports Exerc 1997;29(5 Supplement):249.
- Ziegenfuss T, Lowery LM, and Lemon PW. Acute fluid volume changes in men during three days of creatine supplementation. J Exerc Physiol Online 1998;1(3): .
- Kuehl K, Goldberg L, and Elliot D. Renal insufficiency after creatine supplementation in a college football athlete. Med Sci Sports Exerc 1998;30(5 Suppl ):S235. DOI
- Balsom PD, Ekblom B, Soderlund K, and et al. Creatine supplementation and dynamic high-intensity intermittent excercise. Scand J Med Sci Sports 1993;3:143-149.
- Kirksey KB, Warren BJ, Stone MH, and et al. The effects of six weeks of creatine monohydrate supplementation in male and female track athletes. Med Sci Sports Exerc 1997;29(5 Suppl):S145.
- Kreider R, Ransom J, Rasmussen C, and et al. Creatine supplementation during pre-season football does not affect markers of renal function. 83rd Annual Experimental Biology Meeting 1999;
- Rasmussen C, Kreider R, Ransom J, and et al. Creatine supplementation during pre-season football training does not affect fluid or electrolyte status. 46th Annual American College of Sports Medicine Annual Meeting 1999; DOI
- Tan CW, Hae Tha M, Joo Ng H. Creatine supplementation and venous thrombotic events. Am J Med 2014;127(8):e7-8. PubMed
- Young C, Oladipo O, Frasier S, et al. Hemorrhagic stroke in young healthy male following use of sports supplement Jack3d. Mil Med 2012;177(12):1450-4. PubMed
- Vilella AL, Limsuwat C, Williams DR, Seifert CF. Cholestatic jaundice as a result of combination designer supplement ingestion. Ann Pharmacother 2013;47(7-8):e33. PubMed
- Li N, Hauser R, Holford T, et al. Muscle-building supplement use and increased risk of testicular germ cell cancer in men from Connecticut and Massachusetts. Br J Cancer 2015;112(7):1247-50. PubMed
- Centers for Disease Control and Prevention (CDC). Hyperthermia and dehydration-related deaths associated with rapid weight loss in three collegiate wrestlers - North Carolina, Wisconsin, and Michigan, November-December 1997. MMWR Morb Mortal Wkly Rep 1998
- Litsky F. Collegiate wrestling deaths raise fears about training. The New York Times. December 19, 1997. Available at: http://www.nytimes.com/1997/12/19/sports/wrestling-collegiate-wrestling-deaths-raise-fears-about-training.html.
- The Associated Press. Creatine ruled out in athletes' deaths. The New York Times. May 2, 1998. Available at: http://www.nytimes.com/1998/05/02/sports/plus-college-wrestling-creatine-ruled-out-in-athletes-deaths.html.
- Creatine in the dock. Men's Fitness Magazine (Australia). September 2013. Available at: http://www.mensfitnessmagazine.com.au/2013/09/creatine-in-the-dock/.
- Galvan E, Walker Dk, Simbo SY, et al. Acute and chronic safety and efficacy of dose dependent creatine nitrate supplementation and exercise performance. J Int Soc Sports Nutr. 2016 Mar 31;13:12. PubMed
- Deminice R, Rosa FT, Pfrimer K, Ferrioli E, Jorao AA, Freitas E. Creatine supplementation increases total body water in soccer players: a deuterium oxide dilution study. Int J Sports Med. 2016 Feb;37(2):149-53. PubMed
- Wilkinson TJ, Lemmy AB, Jones AG, et al. Can creatine supplementation improve body composition and objective physical function in Rheumatoid Arthritis patients? A randomized controlled trial. Arthritis Care Res (Hoboken). 2016 Jun;68(6):729-37. PubMed
- Kreider RB, Kalman DS, Antonio J, et al. International Society of Sports Nutrition position stand: safety and efficacy of creating supplementation in exercise, sport, and medicine. J Int Soc Sports Nutr. 2017;14:18.
- de Guingand DL, Palmer KR, Snow RJ, Davies-Tuck ML, Ellery SJ. Risk of adverse outcomes in females taking oral creatine monohydrate: a systematic review and meta-analysis. Nutrients. 2020;12(6):E1780. PubMed
- Almeida D, Colombini A, Machado M. Creatine supplementation improves performance, but is it safe? Double-blind placebo-controlled study. J Sports Med Phys Fitness. 2020;60(7):1034-9. PubMed
- Mills S, Candow DG, Forbes SC, Neary JP, Ormsbee MJ, Antonio J. Effects of creatine supplementation during resistance training sessions in physically active young adults. Nutrients. 2020;12(6):1880. PubMed
- Whinton AK, Donahoe K, Gao R, et al. Repeated application of a novel creatine cream improves muscular peak and average power in male subjects. J Strength Cond Res. 2020;34(9):2482-2491. PubMed
- Dover S, Stephens S, Schneiderman JE, et al. The effect of creatine supplementation on muscle function in childhood myositis: A randomized, double-blind, placebo-controlled feasibility study. J Rheumatol. 2020:jrheum.191375. PubMed
- Chilibeck PD, Candow DG, Landeryou T, Kaviani M, Paus-Jenssen L. Effects of creatine and resistance training on bone health in postmenopausal women. Med Sci Sports Exerc. 2015;47(8):1587-95. PubMed
- Forbes SC, Candow DG, Ostojic SM, Roberts MD, Chilibeck PD. Meta-analysis examining the importance of creatine ingestion strategies on lean tissue mass and strength in older adults. Nutrients 2021;13(6):1912. PubMed
- Silva C, Fung AWS, Masson V, et al. Vitamin D toxicity from an unusual and unexpected source: a report of 2 cases. Horm Res Paediatr 2022. PubMed
- Delpino FM, Figueiredo LM, Forbes SC, Candow DG, Santos HO. Influence of age, sex, and type of exercise on the efficacy of creatine supplementation on lean body mass: A systematic review and meta-analysis of randomized clinical trials. Nutrition 2022;103- PubMed
- Todorovic N, Korovljev D, Stajer V, Jorga J, Ostojic SM. Creatine consumption and liver disease manifestations in individuals aged 12?years and over. Food Sci Nutr 2022;11(2):1134-1141. PubMed
- Robles EL, Pache KM, Gluck JS. Acute compartment syndrome of the leg caused by cocaine use, creatine supplementation and vigorous exercise. J Surg Case Rep 2022;2022(11):rjac502. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC