
Natural Anti Aromatase Support Ingredients & Drug Interactions
by SuperSmart
What is this page for?
First and foremost: checking Natural Anti Aromatase Support against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Natural Anti Aromatase Support is a dietary supplement by SuperSmart with 8 active ingredients. Its ingredients are commonly taken for seasonal allergies, antioxidant support, heart and blood pressure health.Based on those ingredients, 1,302 medications have a known interaction with it, the most serious rated moderate. The ingredients most likely to interact are Quercetin, Genistein, Chrysin. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Natural Anti Aromatase Support by SuperSmart
Ask about any prescription or over-the-counter medication and we check it for interactions with Natural Anti Aromatase Support by SuperSmart — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Natural Anti Aromatase Support by SuperSmart
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
Natural Anti Aromatase Support contains 8 active ingredients. Zinc supports immune function and is effective for zinc deficiency and likely effective for Wilson disease.
Quercetin is a plant compound with limited established evidence for the conditions listed on the label. Chrysin, diindolylmethane (DIM), naringin, genistein, Agaricus bisporus extract, and Epilobium parviflorum extract round out the formula, though evidence for most of these is not established in our data.
The product also contains inactive ingredients including calcium carbonate, stearic acid, maltodextrin, croscarmellose sodium, and shellac.
Does it work?
Strong evidence
Zinc is effective for zinc deficiency and likely effective for Wilson disease — conditions your doctor would diagnose. For other uses listed (acne, age-related macular degeneration, diabetes), zinc is possibly effective, meaning the evidence is suggestive but not conclusive.
For quercetin and chrysin, the evidence we hold rates them as having insufficient reliable evidence for most conditions; we simply don't have enough solid data yet. Diindolylmethane and the remaining ingredients show insufficient evidence as well in our database.
How safe is it?
Well-documented data
Zinc is well tolerated at doses below 40 mg daily (the upper safe limit for adults). At higher doses, it can cause abdominal cramps, nausea, diarrhea, or a metallic taste; long-term high-dose zinc also risks copper deficiency, which may lead to anemia.
Quercetin may cause headache or tingling in some people and is generally well tolerated in typical supplement amounts, though high-dose safety is not well studied. Chrysin appears well tolerated short-term but long-term safety is not established.
Diindolylmethane is generally well tolerated and may cause diarrhea, gas, headache, nausea, or rash; one rare case of a severe drug rash with systemic symptoms has been reported. For pregnancy, we have safety data for diindolylmethane only (rated likely safe), but not for the others — quercetin and chrysin are best avoided during pregnancy due to insufficient safety information.
For breastfeeding, quercetin and chrysin should be avoided, and diindolylmethane has no reliable safety data available.
Meds to double-check
Moderate interaction found
Before taking this product, double-check your use of quinolone and tetracycline antibiotics, cephalexin, penicillamine, blood thinners like warfarin, blood pressure drugs like losartan, cholesterol medications like pravastatin, estrogen therapy or contraceptives, diuretics, and HIV medications. All of these have moderate interactions documented with ingredients in this formula.
No interactions are documented for the four ingredients we could not check.
The bottom line
Scorecard at a glanceFully disclosed formula with strong clinical evidence behind its ingredients' uses. Moderate medication interactions have been identified, and safety information is well characterized.
This product is aimed at hormone-sensitive conditions and contains several ingredients with moderate interactions, especially with antibiotics, blood thinners, and hormone therapies. If you take any prescription medication — particularly antibiotics, blood pressure or cholesterol drugs, blood thinners, or hormones — check your exact medications with the tool on this page before starting.
Talk with your pharmacist or doctor about whether this product fits your individual situation.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 6 of 8 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated May 21, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Natural Anti Aromatase Support, straight from the product label.
| Brand | SuperSmart |
|---|---|
| Barcode (UPC) | 5453003826088 |
| Net contents | 120 Tablet(s) |
| Market status | On market |
| Date entered into DSLD | May 21, 2025 |
| DSLD ID | 332400 |
| Product type | Other Combinations |
| Supplement form | Tablet Or Pill |
| Dietary claims / uses | All Other |
| Intended target group(s) | Adult (18 - 50 Years) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
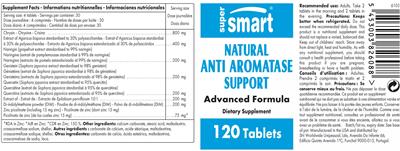
Supplement Facts
The label details for Natural Anti Aromatase Support by SuperSmart, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Zinc | 15 mg | 150% |
| Quercetin | 200 mg | -- |
| Zinc Picolinate | 75 mg | -- |
| Chrysin | 800 mg | -- |
| Diindolylmethane, Powder | 200 mg | -- |
| Naringin | 200 mg | -- |
| Agaricus bisporus Extract | 400 mg | -- |
| Genistein | 200 mg | -- |
| Epilobium parviflorum Extract | 200 mg | -- |
Other ingredients: Calcium Carbonate, Stearic Acid, Maltodextrin, Croscarmellose Sodium, Shellac
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formulation
Advanced formula
FDA Statement of Identity
Dietary Supplement
Suggested/Recommended/Usage/Directions
Recommended use: Adults. Take 2 tablets in the morning and 2 tablets in the evening.
Storage
Precautions: Keeps better when refrigerated.
Store away from direct light, heat and humidity.
Precautions
Do not exceed the recommended daily dose. This product is a nutritional supplement and should not replace a varied, balanced diet.
Keep out of childrens' reach.
As with any nutritional supplement, you should consult a health professional before taking this product if you are pregnant, breastfeeding or have a health problem.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Natural Anti Aromatase Support by SuperSmart label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Natural Anti Aromatase Support by SuperSmart
These are the 8 active ingredients this product is made of. Select any to open its full monograph.
Serving size2 Tablet(s) Dosage formTablet Or Pill Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Quercetin
Interacts with1,169 drugs
Quercetin is a plant flavonoid with antioxidant and anti-inflammatory properties found in many common foods and sold as a supplement. While early rese...
Quercetin monograph & interactionsZinc Picolinate
Interacts with67 drugs
Zinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but suppleme...
Zinc Picolinate monograph & interactions- › Zinc
Chrysin
Interacts with358 drugs
Chrysin is a plant flavonoid sold mainly as a bodybuilding supplement claimed to raise testosterone or block estrogen, but human studies have not show...
Chrysin monograph & interactionsDiindolylmethane, Powder
Interacts with269 drugs
Diindolylmethane (DIM) is a compound made when your body digests cruciferous vegetables, and it is sold as a supplement mainly for hormone balance and...
Diindolylmethane, Powder monograph & interactionsNaringin
Agaricus bisporus Extract
Interacts with86 drugs
Agaricus mushroom (often Agaricus blazei/subrufescens) is a culinary and medicinal mushroom studied mostly for possible immune and antioxidant effects...
Agaricus bisporus Extract monograph & interactionsGenistein
Interacts with867 drugs
Red clover is a plant rich in isoflavones (plant compounds with weak estrogen-like activity) that is most often used for menopause symptoms like hot f...
Genistein monograph & interactionsEpilobium parviflorum Extract
Other (inactive) ingredients: Calcium Carbonate, Stearic Acid, Maltodextrin, Croscarmellose Sodium, Shellac. These complete the product’s ingredient list but are not active constituents.
Natural Anti Aromatase Support by SuperSmart Drug Interactions
HelloPharmacist Interaction Report
Natural Anti Aromatase Support by SuperSmart contains several ingredients with documented interactions.
The most serious finding involves zinc, which moderately reduces absorption of quinolone antibiotics (like ciprofloxacin and levofloxacin). Zinc does this by forming complexes in your gut that prevent both the antibiotic and zinc from being absorbed properly; spacing doses by at least 2 hours before or 4–6 hours after these antibiotics helps.
Read the full breakdown — every affected drug type, severity by severity
Zinc also interacts moderately with cephalexin antibiotics (reducing cephalexin levels by up to 31%), tetracycline antibiotics (reducing absorption by 30–40%), penicillamine, ritonavir, integrase inhibitors used in HIV treatment, and the cancer drug cisplatin. Quercetin, another ingredient here, has moderate interactions with losartan (a blood pressure medication), pravastatin and related cholesterol drugs, warfarin (a blood thinner), cyclosporine, sulfasalazine, and mitoxantrone.
Chrysin may moderately affect estrogen therapy, contraceptive drugs, blood thinners, diclofenac, and aromatase inhibitors. Diindolylmethane potentially moderately interacts with estrogens and diuretics, and may lower levels of certain other medications.
We could not check four ingredients — naringin, Agaricus bisporus extract, genistein, and Epilobium parviflorum extract — because we hold no data for them. Altogether, these interactions span 1,273 individual medications.
Use the medication checker below to verify your exact prescriptions before starting this product.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Natural Anti Aromatase Support?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Natural Anti Aromatase Support interact with 1,302 drugs. Click any drug to see the details.
6 of the 8 ingredients in Natural Anti Aromatase Support interact with drugs. Each result below shows which ingredient is responsible. Quercetin Genistein Chrysin Diindolylmethane, Powder Agaricus bisporus Extract Zinc Picolinate
Ado-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with Natural Anti Aromatase Support — through 2 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Ado-trastuzumab Emtansine interactionGenisteinCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP3A4; however, a small clinical study found no effect.
Read the full Genistein + Ado-trastuzumab Emtansine interactionAbciximabReoPro
How Abciximab interacts with Natural Anti Aromatase Support — through 2 ingredients. Tap an ingredient for the detail:
ChrysinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, chrysin might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full Chrysin + Abciximab interactionGenisteinAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Although some laboratory research suggests that red clover may have anticoagulant and antiplatelet activity, clinical research has not shown this effect.
Read the full Genistein + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with Natural Anti Aromatase Support — through 2 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Abemaciclib interactionGenisteinCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP3A4; however, a small clinical study found no effect.
Read the full Genistein + Abemaciclib interactionAbiraterone
How Abiraterone interacts with Natural Anti Aromatase Support — through 2 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Abiraterone interactionGenisteinCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP3A4; however, a small clinical study found no effect.
Read the full Genistein + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with Natural Anti Aromatase Support — through 2 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Abiraterone Acetate interactionGenisteinCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP3A4; however, a small clinical study found no effect.
Read the full Genistein + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with Natural Anti Aromatase Support — through 3 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 2c9 (cyp2c9) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2C9 substrates.
Read the full Quercetin + Abrocitinib interactionChrysinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, chrysin might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full Chrysin + Abrocitinib interactionGenisteinCytochrome P450 2c19 (cyp2c19) Substrates, Cytochrome P450 2c9 (cyp2c9) Substrates +1 Minor
Interaction Summary
Theoretically, red clover might increase the levels and clinical effects of drugs metabolized by CYP2C19.
Read the full Genistein + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with Natural Anti Aromatase Support — through 2 ingredients. Tap an ingredient for the detail:
QuercetinP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of P-glycoprotein substrates.
Read the full Quercetin + Acalabrutinib interactionGenisteinCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP3A4; however, a small clinical study found no effect.
Read the full Genistein + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Natural Anti Aromatase Support — through 2 ingredients. Tap an ingredient for the detail:
QuercetinAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, concomitant use of quercetin and antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Quercetin + Acarbose interactionAgaricus Bisporus ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking agaricus mushroom with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Agaricus Bisporus Extract + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Natural Anti Aromatase Support — through 1 ingredient. Tap an ingredient for the detail:
QuercetinAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking quercetin with antihypertensive drugs might increase the risk of hypotension.
Read the full Quercetin + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Natural Anti Aromatase Support — through 2 ingredients. Tap an ingredient for the detail:
ChrysinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, chrysin might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full Chrysin + Acenocoumarol interactionGenisteinAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Although some laboratory research suggests that red clover may have anticoagulant and antiplatelet activity, clinical research has not shown this effect.
Read the full Genistein + Acenocoumarol interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinOrganic Anion Transporter 3 (oat3) Substrates, Organic Anion Transporter 1 (oat1) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the effects and adverse effects of OAT3 substrates.
Read the full Quercetin + Acetaminophen, Aspirin interactionChrysinAnticoagulant/antiplatelet Drugs, Glucuronidated Drugs +1 Moderate
Interaction Summary
Theoretically, chrysin might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full Chrysin + Acetaminophen, Aspirin interactionGenisteinCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP1A2; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Aspirin interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
ChrysinCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, chrysin might increase levels of drugs metabolized by CYP1A2.
Read the full Chrysin + Acetaminophen, Aspirin, Caffeine interactionQuercetinOrganic Anion Transporter 1 (oat1) Substrates, Organic Anion Transporter 3 (oat3) Substrates +1 Moderate
Interaction Summary
Theoretically, concomitant use might increase the effects and adverse effects of OAT1 substrates.
Read the full Quercetin + Acetaminophen, Aspirin, Caffeine interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Aspirin, Caffeine interactionGenisteinAnticoagulant/antiplatelet Drugs, Caffeine +2 Minor
Interaction Summary
Although some laboratory research suggests that red clover may have anticoagulant and antiplatelet activity, clinical research has not shown this effect.
Read the full Genistein + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Butalbital, Caffeine interactionChrysinCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Minor
Interaction Summary
Theoretically, chrysin might increase levels of drugs metabolized by CYP1A2.
Read the full Chrysin + Acetaminophen, Butalbital, Caffeine interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Butalbital, Caffeine interactionGenisteinCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP1A2; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Butalbital, Caffeine, Codeine interactionGenisteinCaffeine, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Minor
Interaction Summary
Theoretically, soy might reduce the clearance of caffeine; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Butalbital, Caffeine, Codeine interactionChrysinGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, chrysin might increase the clearance of drugs that are UGT1A1 substrates, thereby reducing their effectiveness.
Read the full Chrysin + Acetaminophen, Butalbital, Caffeine, Codeine interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Quercetin + Acetaminophen, Butalbital, Codeine interactionGenisteinCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP1A2; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Butalbital, Codeine interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Butalbital, Codeine interactionChrysinGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, chrysin might increase the clearance of drugs that are UGT1A1 substrates, thereby reducing their effectiveness.
Read the full Chrysin + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Quercetin + Acetaminophen, Butalbital, Codeine Phosphate interactionChrysinCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Minor
Interaction Summary
Theoretically, chrysin might increase levels of drugs metabolized by CYP1A2.
Read the full Chrysin + Acetaminophen, Butalbital, Codeine Phosphate interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Butalbital, Codeine Phosphate interactionGenisteinCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP1A2; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Quercetin + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionGenisteinCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP1A2; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionChrysinGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, chrysin might increase the clearance of drugs that are UGT1A1 substrates, thereby reducing their effectiveness.
Read the full Chrysin + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Caffeine, Codeine interactionGenisteinCaffeine, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Minor
Interaction Summary
Theoretically, soy might reduce the clearance of caffeine; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Caffeine, Codeine interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Caffeine, Codeine interactionChrysinGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, chrysin might increase the clearance of drugs that are UGT1A1 substrates, thereby reducing their effectiveness.
Read the full Chrysin + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Quercetin + Acetaminophen, Caffeine, Codeine, Salicylamide interactionChrysinCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Minor
Interaction Summary
Theoretically, chrysin might increase levels of drugs metabolized by CYP1A2.
Read the full Chrysin + Acetaminophen, Caffeine, Codeine, Salicylamide interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Caffeine, Codeine, Salicylamide interactionGenisteinCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP1A2; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Caffeine, Dihydrocodeine interactionGenisteinCaffeine, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Minor
Interaction Summary
Theoretically, soy might reduce the clearance of caffeine; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Caffeine, Dihydrocodeine interactionChrysinGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, chrysin might increase the clearance of drugs that are UGT1A1 substrates, thereby reducing their effectiveness.
Read the full Chrysin + Acetaminophen, Caffeine, Dihydrocodeine interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Caffeine, IsomethepteneMigralam
How Acetaminophen, Caffeine, Isometheptene interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Caffeine, Isometheptene interactionGenisteinCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP1A2; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Caffeine, Isometheptene interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Caffeine, Isometheptene interactionChrysinGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, chrysin might increase the clearance of drugs that are UGT1A1 substrates, thereby reducing their effectiveness.
Read the full Chrysin + Acetaminophen, Caffeine, Isometheptene interactionAcetaminophen, Caffeine, PyrilamineMidol Max Strength Menstrual
How Acetaminophen, Caffeine, Pyrilamine interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
Diindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates, Diuretic Drugs Moderate
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Caffeine, Pyrilamine interactionQuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Caffeine, Pyrilamine interactionChrysinCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Minor
Interaction Summary
Theoretically, chrysin might increase levels of drugs metabolized by CYP1A2.
Read the full Chrysin + Acetaminophen, Caffeine, Pyrilamine interactionGenisteinCaffeine, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Minor
Interaction Summary
Theoretically, soy might reduce the clearance of caffeine; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Caffeine, Pyrilamine interactionAcetaminophen, Chlorpheniramine Maleate, Dextromethorphan HbrVicks Formula 44M Cough, Cold & Flu Relief
How Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Quercetin + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionGenisteinCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP1A2; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionChrysinGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, chrysin might increase the clearance of drugs that are UGT1A1 substrates, thereby reducing their effectiveness.
Read the full Chrysin + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Quercetin + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionGenisteinCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP1A2; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionChrysinCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Minor
Interaction Summary
Theoretically, chrysin might increase levels of drugs metabolized by CYP1A2.
Read the full Chrysin + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionAcetaminophen, Chlorpheniramine, DextromethorphanCoricidin II Extra Strength Cold and Flu
How Acetaminophen, Chlorpheniramine, Dextromethorphan interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Quercetin + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionChrysinGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, chrysin might increase the clearance of drugs that are UGT1A1 substrates, thereby reducing their effectiveness.
Read the full Chrysin + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionGenisteinCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP1A2; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionAcetaminophen, Chlorpheniramine, Dextromethorphan HydrobromideCoricidin HBP Maximum Strength Flu
How Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionGenisteinCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP3A4; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionChrysinCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Minor
Interaction Summary
Theoretically, chrysin might increase levels of drugs metabolized by CYP1A2.
Read the full Chrysin + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionAcetaminophen, Chlorpheniramine, Dextromethorphan, PhenylpropanolamineMulti Symptom Cold Relief
How Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Quercetin + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionGenisteinCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP1A2; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionChrysinCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Minor
Interaction Summary
Theoretically, chrysin might increase levels of drugs metabolized by CYP1A2.
Read the full Chrysin + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionAcetaminophen, Chlorpheniramine, Dextromethorphan, PseudoephedrineChildren's Tylenol Cold Plus Cough, Tylenol Cold Ex Strength
How Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interactionChrysinGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, chrysin might increase the clearance of drugs that are UGT1A1 substrates, thereby reducing their effectiveness.
Read the full Chrysin + Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interactionGenisteinCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP3A4; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interactionAcetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, SalicylamideRhinogesic GG
How Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interactionGenisteinCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP1A2; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interactionChrysinGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, chrysin might increase the clearance of drugs that are UGT1A1 substrates, thereby reducing their effectiveness.
Read the full Chrysin + Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interactionAcetaminophen, Chlorpheniramine, PhenylephrineAlka-Seltzer PLUS, Histex SR, Protid
How Acetaminophen, Chlorpheniramine, Phenylephrine interacts with Natural Anti Aromatase Support — through 4 ingredients. Tap an ingredient for the detail:
QuercetinCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Quercetin + Acetaminophen, Chlorpheniramine, Phenylephrine interactionGenisteinCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, red clover might increase levels of drugs metabolized by CYP1A2; however, a small clinical study found no effect.
Read the full Genistein + Acetaminophen, Chlorpheniramine, Phenylephrine interactionChrysinCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Minor
Interaction Summary
Theoretically, chrysin might increase levels of drugs metabolized by CYP1A2.
Read the full Chrysin + Acetaminophen, Chlorpheniramine, Phenylephrine interactionDiindolylmethane, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
Read the full Diindolylmethane, Powder + Acetaminophen, Chlorpheniramine, Phenylephrine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Natural Anti Aromatase Support with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Quercetin
Antidiabetes Drugs
Theoretically, concomitant use of quercetin and antidiabetes drugs might increase the risk of hypoglycemia.
Clinical research suggests that a combination of quercetin, myricetin, and chlorogenic acid reduce levels of fasting glucose in patients with type 2 diabetes, including those already taking antidiabetes agents. The effect of quercetin alone is unknown.
Antihypertensive Drugs
Theoretically, taking quercetin with antihypertensive drugs might increase the risk of hypotension.
Quercetin can modestly decrease blood pressure in people with mild hypertension. Theoretically, it might have additive blood pressure lowering effects when used with antihypertensive drugs.
Cyclosporine (Neoral, Sandimmune)
Theoretically, concomitant use might increase the levels and adverse effects of cyclosporine.
A small study in healthy volunteers shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of a single dose of cyclosporine, possibly due to inhibition of p-glycoprotein or cytochrome P450 3A4 (CYP3A4), which metabolizes cyclosporin.
Cytochrome P450 2C8 (Cyp2C8) Substrates
Theoretically, concomitant use might increase the levels and adverse effects of CYP2C8 substrates.
In vitro research shows that quercetin inhibits CYP2C8. Inhibition of paclitaxel (Taxol) metabolism via CYP2C8 has been reported in vitro. However, a small study in humans found no effect of quercetin on rosiglitazone (Avandia), which is also a CYP2C8 substrate.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, concomitant use might increase the levels and adverse effects of CYP2C9 substrates.
A small clinical study in healthy volunteers shows that taking quercetin 500 mg twice daily for 10 days prior to taking diclofenac, a CYP2C9 substrate, increases diclofenac plasma levels by 75% and prolongs the half-life by 32.5%. Animal research also shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of losartan (Cozaar), a substrate of CYP2C9. Furthermore, laboratory research shows that quercetin inhibits CYP2C9.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
In vitro research show that quercetin inhibits CYP2D6. This effect has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
A small clinical study in healthy volunteers shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of a single dose of cyclosporine (Neoral, Sandimmune), a substrate of CYP3A4. Animal research also shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of losartan (Cozaar) and quetiapine (Seroquel), substrates of CYP3A4. Other laboratory research also shows that quercetin inhibits CYP3A4. However, one clinical study shows that quercetin can increase the metabolism of midazolam, a substrate of CYP3A4, and decrease serum concentrations of midazolam by about 24% in some healthy individuals, suggesting possible induction of CYP3A4.
Diclofenac (Voltaren, Others)
Theoretically, concomitant use might increase the levels and adverse effects of diclofenac.
A small clinical study in healthy volunteers shows that taking quercetin 500 mg twice daily for 10 days prior to taking diclofenac increases diclofenac plasma levels by 75% and prolongs the half-life by 32.5%. This is thought to be due to inhibition of CYP2C9 by quercetin.
Losartan (Cozaar)
Theoretically, concomitant use might increase the effects and adverse effects of losartan and decrease the effects of its active metabolite.
Animal research shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of losartan (Cozaar) while decreasing plasma levels of losartan's active metabolite. This metabolite, which is around 10-fold more potent than losartan, is the result of cytochrome P450 (CYP) 2C9- and CYP3A4-mediated transformation of losartan. Additionally, in vitro research shows that quercetin may inhibit P-glycoprotein-mediated efflux of losartan from the intestines, resulting in increased absorption of losartan. These results suggest that concomitant use of quercetin and losartan might increase systemic exposure to losartan while also decreasing plasma concentrations of losartan's active and more potent metabolite.
Midazolam (Versed)
Theoretically, concomitant use might decrease the levels and effects of midazolam.
A small clinical study in healthy volunteers shows that quercetin can increase the metabolism of midazolam, with a decrease in AUC of about 24%.
Mitoxantrone
Theoretically, quercetin might increase the effects and adverse effects of mitoxantrone.
In vitro research shows that quercetin increases the intracellular accumulation and cytotoxicity of mitoxantrone, possibly through inhibition of breast cancer resistance protein (BCRP), of which mitoxantrone is a substrate. So far, this interaction has not been reported in humans.
Organic Anion Transporter 1 (Oat1) Substrates
Theoretically, concomitant use might increase the effects and adverse effects of OAT1 substrates.
In vitro research shows that quercetin is a strong non-competitive inhibitor of OAT1, with half-maximal inhibitory concentration (IC50) values less than 10 mcM. So far, this interaction has not been reported in humans.
Organic Anion Transporter 3 (Oat3) Substrates
Theoretically, concomitant use might increase the effects and adverse effects of OAT3 substrates.
In vitro research shows that quercetin is a strong non-competitive inhibitor of OAT3, with half-maximal inhibitory concentration (IC50) values as low as 0.75 mcM. So far, this interaction has not been reported in humans.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Theoretically, concomitant use might increase the effects and adverse effects of OATP substrates.
In vitro evidence shows that quercetin can inhibit organic anion-transporting peptide (OATP) 1B1-mediated uptake of estrone-3-sulfate and pravastatin. Furthermore, clinical research in healthy males shows that intake of quercetin along with pravastatin increases the AUC of pravastatin by 24%, prolongs its half-life by 14%, and decreases its apparent clearance by 18%, suggesting that quercetin modestly inhibits the uptake of pravastatin in hepatic cells.
P-Glycoprotein Substrates
Theoretically, concomitant use might alter the effects and adverse effects of P-glycoprotein substrates.
There is preliminary evidence that quercetin inhibits the gastrointestinal P-glycoprotein efflux pump, which might increase the bioavailability and serum levels of drugs transported by the pump. A small study in healthy volunteers reported that pretreatment with quercetin increased bioavailability and plasma levels after a single dose of cyclosporine (Neoral, Sandimmune). Also, two small studies have shown that quercetin might decrease the absorption of talinolol, a substrate transported by the gastrointestinal P-glycoprotein efflux pump. However, in another small study, several days of quercetin treatment did not significantly affect the pharmacokinetics of saquinavir (Invirase). The reason for these discrepancies is not entirely clear. Until more is known, use quercetin cautiously in combination with P-glycoprotein substrates.
Pravastatin (Pravachol)
Theoretically, concomitant use might increase the effects and adverse effects of pravastatin.
In vitro evidence shows that quercetin can inhibit OATP 1B1-mediated uptake of pravastatin. Also, preliminary clinical research in healthy males shows that intake of quercetin along with pravastatin increases the maximum concentration of pravastatin by 24%, prolongs its half-life by 14%, and decreases its apparent clearance by 18%, suggesting that quercetin modestly inhibits the uptake of pravastatin in hepatic cells.
Prazosin (Minipress)
Theoretically, quercetin might increase the effects and adverse effects of prazosin.
In vitro research shows that quercetin inhibits the transcellular efflux of prazosin, possibly through inhibition of breast cancer resistance protein (BCRP), of which prazosin is a substrate. BCRP is an ATP-binding cassette efflux transporter in the intestines, kidneys, and liver. So far, this interaction has not been reported in humans.
Quetiapine (Seroquel)
Theoretically, concomitant use might increase the effects and adverse effects of quetiapine.
Animal research shows that pretreatment with quercetin can increase plasma levels of quetiapine and prolong its clearance, possibly due to inhibition of cytochrome P450 3A4 (CYP3A4) by quercetin. Additionally, the brain-to-plasma ratio of quetiapine concentrations increased, possibly due to inhibition of P-glycoprotein at the blood-brain barrier. This interaction has not been reported in humans.
Quinolone Antibiotics
Theoretically, concomitant use might inhibit the effects of quinolone antibiotics.
In vitro, quercetin binds to the DNA gyrase site on bacteria, which may interfere with the activity of quinolone antibiotics.
Sulfasalazine (Azulfidine)
Theoretically, quercetin might increase the effects and adverse effects of sulfasalazine.
Animal research shows that quercetin increases the maximum serum concentration (Cmax) and area under the curve (AUC) of sulfasalazine, possibly through inhibition of breast cancer resistance protein (BCRP), of which sulfasalazine is a substrate. So far, this interaction has not been reported in humans.
Warfarin (Coumadin)
Theoretically, quercetin may increase the risk of bleeding if used with warfarin.
Animal and in vitro studies show that quercetin might increase serum levels of warfarin. Quercetin and warfarin have the same human serum albumin (HSA) binding site, and in vitro research shows that quercetin has stronger affinity for the HSA binding site and can theoretically displace warfarin, causing higher serum levels of warfarin. Animal research shows that taking quercetin for 2 weeks before initiating warfarin increases the maximum serum level of warfarin by 30%, the half-life by 10%, and the overall exposure by 63% when compared with control. Concomitant administration of quercetin and warfarin, without quercetin pre-treatment, also increased these measures, but to a lesser degree. Researchers theorize that inhibition of CYP3A4 by quercetin may explain these effects. So far, this interaction has not been reported in humans.
Genistein
Estrogens
Theoretically, concomitant use of large amounts of red clover might interfere with estrogen therapy.
Red clover contains phytoestrogens which might have estrogenic activity in some people. Theoretically, red clover might compete for estrogen receptors and interfere with estrogen-containing drug therapy.
Methotrexate (Trexall, Others)
Theoretically, red clover might increase the risk of methotrexate toxicity.
In a case report, a 52-year-old female receiving weekly methotrexate injections for psoriasis developed symptoms of methotrexate toxicity, including severe vomiting and epigastric pain, after three days of taking red clover 430 mg daily. Toxicity resolved after red clover was discontinued. However, no liver function tests or methotrexate levels were reported.
Tamoxifen (Nolvadex)
Theoretically, the phytoestrogens in red clover might interfere with tamoxifen.
In vitro and animal research suggests that genistein, a constituent of red clover, might antagonize the antitumor effects of tamoxifen. However, there is some evidence from an animal study that red clover does not reduce the efficacy of tamoxifen. Until more is known, tell patients taking tamoxifen to avoid red clover.
Anticoagulant/Antiplatelet Drugs
Although some laboratory research suggests that red clover may have anticoagulant and antiplatelet activity, clinical research has not shown this effect.
In vitro research suggests that genistein in red clover has antiplatelet effects, and historically, red clover was thought to have anticoagulant effects due to its coumarin content. However, some experts state that this is unlikely as most natural coumarins have not been shown to have anticoagulant effects, and their content in red clover is low. Additionally, some clinical research in postmenopausal patients found no effect on coagulation or prothrombin time with the use of red clover flowering tops 378 mg daily for 12 months or red clover isoflavone (Rimostil) 50 mg daily for 2 years.
Caffeine
Theoretically, soy might reduce the clearance of caffeine; however, a small clinical study found no effect.
Red clover contains genistein. Taking genistein 1 gram daily for 14 days seems to inhibit caffeine clearance and metabolism in healthy females. However, this effect does not seem to occur with the lower amounts of genistein found in red clover. A clinical study in healthy postmenopausal individuals shows that taking red clover capsules standardized to contain 60 mg isoflavones twice daily for 14 days does not affect the pharmacokinetics of caffeine.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, red clover might increase levels of drugs metabolized by CYP1A2; however, a small clinical study found no effect.
In vitro evidence shows that red clover inhibits CYP1A2. However, a clinical study in healthy postmenopausal individuals shows that taking red clover capsules standardized to contain 60 mg isoflavones twice daily for 14 days does not affect the pharmacokinetics of caffeine, a CYP1A2 probe substrate.
Cytochrome P450 2C19 (Cyp2C19) Substrates
Theoretically, red clover might increase the levels and clinical effects of drugs metabolized by CYP2C19.
In vitro evidence suggests that red clover weakly inhibits CYP2C19. This interaction has not been reported in humans.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, red clover might increase levels of drugs metabolized by CYP2C9; however, a small clinical study found no effect.
In vitro evidence suggests that red clover might inhibit CYP2C9. However, a clinical study in healthy postmenopausal individuals shows that taking red clover capsules standardized to contain 60 mg isoflavones twice daily for 14 days does not affect the pharmacokinetics of tolbutamide, a CYP2C9 probe substrate.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, red clover might increase levels of drugs metabolized by CYP3A4; however, a small clinical study found no effect.
In vitro evidence shows that red clover might inhibit CYP3A4 isoenzymes. However, a clinical study in healthy postmenopausal individuals shows that taking red clover capsules standardized to contain 60 mg isoflavones twice daily for 14 days does not affect the pharmacokinetics of alprazolam, a CYP3A4 probe substrate.
Chrysin
Anticoagulant/Antiplatelet Drugs
Theoretically, chrysin might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
In vitro evidence suggests that chrysin might inhibit platelet aggregation.
Aromatase Inhibitors
Theoretically, chrysin might increase the effects and adverse effects of aromatase inhibitors.
In vitro research suggests that chrysin might decrease estrogen synthesis by acting as an aromatase (estrogen synthetase) inhibitor..
Contraceptive Drugs
Theoretically, chrysin might reduce the efficacy of estrogen-containing contraceptive drugs.
In vitro research suggests that chrysin might have antiestrogenic activity.
Diclofenac (Voltaren, Others)
Theoretically, chrysin might increase the effects and adverse effects of diclofenac.
In vitro research suggests that chrysin and its sulfate conjugate inhibit diclofenac metabolism. It is speculated that chrysin and its sulfate conjugate reduce the metabolism of diclofenac by inhibiting cytochrome P450 2C9. This effect has not been reported in humans.
Estrogens
Theoretically, chrysin might decrease the effects of estrogen therapy.
In vitro research suggests that chrysin might have antiestrogenic activity.
Mephenytoin (Mesantoin)
Theoretically, chrysin might increase the effects and adverse effects of mephenytoin.
In vitro research suggests that chrysin and its sulfate and glucuronide conjugates inhibit S-mephenytoin metabolism. It is speculated that chrysin and its conjugates reduce the metabolism of S-mephenytoin by inhibiting cytochrome P450 2C19. This effect has not been reported in humans.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, chrysin might increase levels of drugs metabolized by CYP1A2.
In vitro research suggests that chrysin inhibits CYP1A2 isozymes. However, chrysin does not appear to inhibit CYP1A2-dependent caffeine metabolism in animals. Due to chrysin's low bioavailability and rapid metabolism to glucuronide and sulfate conjugates, this interaction is unlikely.
Glucuronidated Drugs
Theoretically, chrysin might increase the clearance of drugs that are UGT1A1 substrates, thereby reducing their effectiveness.
In vitro research suggests that chrysin might induce UDP-glucuronosyltransferase 1A1 (UGT1A1).
Testosterone
Theoretically, chrysin might increase the effects and adverse effects of testosterone.
In vitro research suggests that chrysin and its sulfate conjugate inhibit testosterone metabolism. It is speculated that chrysin and its sulfate conjugate reduce the metabolism of testosterone by inhibiting cytochrome P450 3A4. This effect has not been reported in humans.
Diindolylmethane, Powder
Diuretic Drugs
Theoretically, diindolylmethane might increase the risk of hyponatremia if used with sodium-depleting diuretics.
Large doses of diindolylmethane (600 mg daily) have been associated with two cases of asymptomatic hyponatremia in clinical research.
Estrogens
Theoretically, diindolylmethane might increase or decrease the effects of estrogens.
Diindolylmethane might have mild estrogenic or antiestrogenic effects. Theoretically, large amounts of diindolylmethane might interfere with hormone replacement therapy.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, diindolylmethane might lower serum levels of CYP1A2 substrates.
In vitro evidence suggests that diindolylmethane can induce CYP1A2. Theoretically, it might increase metabolism of CYP1A2 substrates and lower serum concentrations. This interaction has not been reported in humans.
Agaricus bisporus Extract
Antidiabetes Drugs
Theoretically, taking agaricus mushroom with antidiabetes drugs might increase the risk of hypoglycemia.
In one clinical study in patients with type 2 diabetes who are stabilized on conventional oral hypoglycemic agents, 3 of 29 patients taking an agaricus mushroom extract 500 mg three times daily for 12 weeks reported hypoglycemia, compared to one of 29 patients in the placebo group.
Zinc Picolinate
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Theoretically, zinc might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after zinc containing products.
Cephalexin (Keflex)
Zinc might decrease cephalexin levels by chelating with cephalexin in the gut and preventing its absorption.
A pharmacokinetic study shows that zinc sulfate 250 mg taken concomitantly with cephalexin 500 mg decreases peak levels of cephalexin by 31% and reduces the exposure to cephalexin by 27%. Also, taking zinc sulfate 3 hours before cephalexin decreases peak levels of cephalexin by 11% and reduces the exposure to cephalexin by 18%. By decreasing cephalexin levels, zinc might increase the risk of treatment failure. This effect does not occur when zinc is taken 3 hours after the cephalexin dose. To avoid an interaction, advise patients take zinc sulfate 3 hours after taking cephalexin.
Cisplatin (Platinol-Aq)
Theoretically, zinc might interfere with the therapeutic effects of cisplatin.
Animal research suggests that zinc stimulates tumor cell production of the protein metallothionein, which binds and inactivates cisplatin. It is not known whether zinc supplements or high dietary zinc intake can cause clinically significant interference with cisplatin therapy. Cisplatin might also increase zinc excretion.
Integrase Inhibitors
Theoretically, taking zinc along with integrase inhibitors might decrease the levels and clinical effects of these drugs.
Zinc is a divalent cation. Pharmacokinetic studies have shown that other divalent cations such as calcium and iron can decrease blood levels of the integrase inhibitor dolutegravir through chelation.
Penicillamine (Cuprimine, Depen)
Zinc might reduce the levels and clinical effects of penicillamine.
By forming an insoluble complex with penicillamine, zinc interferes with penicillamine absorption and activity. Zinc supplements reduce the efficacy of low-dose penicillamine (0.5-1 gram/day), but do not seem to affect higher doses (1-2.75 gram/day), provided dosing times are separated. Advise patients to take zinc and penicillamine at least 2 hours apart.
Quinolone Antibiotics
Zinc can decrease the levels and clinical effects of quinolones antibiotics.
Quinolones form complexes with zinc in the gastrointestinal tract, reducing absorption of both the quinolone and zinc if taken at the same time. Advise patients to take these drugs at least 2 hours before, or 4-6 hours after, zinc supplements.
Ritonavir (Norvir)
Zinc modestly reduces levels of ritonavir.
Clinical research shows that zinc might reduce serum ritonavir levels by chelating with ritonavir in the gut and preventing its absorption. In patients with HIV, ritonavir is taken with atazanavir to prevent the metabolism and increase the effects of atazanavir. A pharmacokinetic study shows that, in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate (Solvazinc tablets) 125 mg as a single dose or as multiple daily doses for 2 weeks reduces plasma levels of ritonavir by about 16%. However, atazanavir levels still remains high enough to prevent HIV virus replication. Therefore, the decrease in ritonavir levels is not likely to be clinically significant.
Tetracycline Antibiotics
Zinc might reduce levels of tetracycline antibiotics.
Tetracyclines form complexes with zinc in the gastrointestinal tract, which can reduce absorption of both the tetracycline and zinc when taken at the same time. Taking zinc sulfate 200 mg with tetracycline reduces absorption of the antibiotic by 30% to 40%. Demeclocycline and minocycline cause a similar interaction. However, doxycycline does not seem to interact significantly with zinc. Advise patients to take tetracyclines at least 2 hours before, or 4-6 hours after, zinc supplements to avoid any interactions.
Amiloride (Midamor)
Amiloride can modestly reduce zinc excretion and increase zinc levels.
Clinical research shows that amiloride can reduce urinary zinc excretion, especially at doses of 10 mg per day or more. This zinc-sparing effect can help to counteract zinc losses caused by thiazide diuretics, but it is unlikely to cause zinc toxicity at usual amiloride doses. The other potassium-sparing diuretics, spironolactone (Aldactone) and triamterene (Dyrenium), do not seem to have a zinc-sparing effect.
Atazanavir (Reyataz)
Zinc modestly reduces levels of atazanavir, although this effect does not seem to be clinically significant.
Clinical research shows that zinc might decrease serum atazanavir levels by chelating with atazanavir in the gut and preventing its absorption. Although a single dose of zinc sulfate (Solvazinc tablets) 125 mg orally does not affect atazanavir concentrations in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate 125 mg daily for 2 weeks reduces plasma levels of atazanavir by about 22% in these patients. However, despite this decrease, atazanavir levels still remain at high enough concentrations for the prevention of HIV virus replication.
Brand information
Manufacturer and brand details for Natural Anti Aromatase Support, from the product label.
SuperSmart
See all SuperSmart products- Name
- SN Worldwide Unipessoal, Lda
- Street Address
- Avenida Do Infante 66, Edificio Quinta Avenida 1 C
- City
- Funchal
- ZipCode
- 9000-015
Natural Anti Aromatase Support by SuperSmart: Common Questions
Does Natural Anti Aromatase Support by SuperSmart interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Is zinc in this product safe to take with my antibiotic?
Can I take this if I'm on a blood thinner like warfarin?
What does zinc actually do in this formula?
Is it safe to take while pregnant?
What are the most common side effects?
Does this work for hormone-related concerns?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Natural Anti Aromatase Support is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Natural Anti Aromatase Support’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Quercetin
Interacts with 1,169 drugsQuercetin is a plant flavonoid with antioxidant and anti-inflammatory properties found in many common foods and sold as a supplement. While early research is interesting for allergies, blood...
Read the full Quercetin monograph → Herb & supplement monographZinc
Interacts with 67 drugsZinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but supplements can help correct or prevent a defici...
Read the full Zinc monograph → Herb & supplement monographChrysin
Interacts with 358 drugsChrysin is a plant flavonoid sold mainly as a bodybuilding supplement claimed to raise testosterone or block estrogen, but human studies have not shown these benefits, largely because the bo...
Read the full Chrysin monograph → Herb & supplement monographDiindolylmethane
Interacts with 269 drugsDiindolylmethane (DIM) is a compound made when your body digests cruciferous vegetables, and it is sold as a supplement mainly for hormone balance and cancer prevention. Although early lab s...
Read the full Diindolylmethane monograph → Herb & supplement monographAgaricus Mushroom
Interacts with 86 drugsAgaricus mushroom (often Agaricus blazei/subrufescens) is a culinary and medicinal mushroom studied mostly for possible immune and antioxidant effects. The human evidence is limited and not...
Read the full Agaricus Mushroom monograph → Herb & supplement monographRed Clover
Interacts with 867 drugsRed clover is a plant rich in isoflavones (plant compounds with weak estrogen-like activity) that is most often used for menopause symptoms like hot flashes. The evidence is mixed and genera...
Read the full Red Clover monograph →Sources & How We Checked
Natural Anti Aromatase Support's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 180 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Zinc 88 references
- Barceloux DG. Zinc. J Toxicol Clin Toxicol 1999;37:279-92.
- Eby GA, Davis DR, Halcomb WW. Reduction in duration of common colds by zinc gluconate lozenges in a double-blind study. Antimicrob Agents Chemother 1984;25:20-4. DOI
- Smith DS, Helzner EC, Nuttall CE Jr, et al. Failure of zinc gluconate in treatment of acute upper respiratory tract infections. Antimicrob Agents Chemother 1989;33:646-8. PubMed
- Blondeau JM. Expanded activity and utility of the new fluoroquinolones: a review. Clin Ther 1999;21:3-40. PubMed
- Reyes AJ, Olhaberry JV, Leary WP, et al. Urinary zinc excretion, diuretics, zinc deficiency and some side-effects of diuretics. S Afr Med J 1983;64:936-41.
- Kugelmas M. Preliminary observation: oral zinc sulfate replacement is effective in treating muscle cramps in cirrhotic patients. J Am Coll Nutr 2000;19:13-5. PubMed
- Hebel SK, ed. Drug Facts and Comparisons. 52nd ed. St. Louis: Facts and Comparisons, 1998.
- Chan S, Gerson B, Subramaniam S. The role of copper, molybdenum, selenium, and zinc in nutrition and health. Clin Lab Med 1998;18:673-85. DOI
- Brewer GJ, Yuzbasiyan-Gurkan V, Johnson V, et al. Treatment of Wilson's disease with zinc: XI. Interaction with other anticopper agents. J Am Coll Nutr 1993;12:26-30. PubMed
- Fosmire GJ. Zinc toxicity. Am J Clin Nutr 1990;51:225-7.
- Lomaestro BM, Bailie GR. Absorption interactions with fluoroquinolones. 1995 update. Drug Saf 1995;12:314-33. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Seelig MS. Auto-immune complications of D-penicillamine - A possible result of zinc and magnesium depletion and of pyridoxine inactivation. J Am Coll Nutr 1982;1:207-14. PubMed
- Neuvonen PJ. Interactions with the absorption of tetracyclines. Drugs 1976;11:45-54.. PubMed
- Hirt M, Nobel S, Barron E. Zinc nasal gel for the treatment of common cold symptoms: A double-blind, placebo-controlled trial. Ear Nose Throat J 2000;79:778-82.. DOI
- Simkin PA. Oral zinc sulphate in rheumatoid arthritis. Lancet 1976;2:539-42. PubMed
- Wray D. A double-blind trial of systemic zinc sulfate in recurrent aphthous stomatitis. Oral Surg Oral Med Oral Pathol 1982;53:469-72. PubMed
- Douglas RM, Miles HB, Moore BW, et al. Failure of effervescent zinc acetate lozenges to alter the course of upper respiratory tract infections in Australian adults. Antimicrob Agents Chemother 1987;31:1263-5. PubMed
- Lagiou P, Wuu J, Trichopoulou A, et al. Diet and benign prostatic hyperplasia: a study in Greece. Urology 1999;54:284-90. PubMed
- Ewing CI, Gibbs AC, Ashcroft C, David TJ. Failure of oral zinc supplementation in atopic eczema. Eur J Clin Nutr 1991;45:507-10.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Age-Related Eye Disease Study Research Group. A randomized, placebo-controlled, clinical trial of high-dose supplementation with vitamins C and E, beta carotene, and zinc for age-related macular degeneration and vision loss. AREDS report no. 8. Arch Oph
- Greenberg JE, Lynn M, Kirsner RS, et al. Mucocutaneous pigmented macule as a result of zinc deposition. J Cutan Pathol 2002;29:613-5. PubMed
- Godfrey HR, Godfrey NJ, Godfrey JC, Riley D. A randomized clinical trial on the treatment of oral herpes with topical zinc oxide/glycine. Altern Ther Health Med 2001;7:49-56.
- Turner RB. Ineffectiveness of intranasal zinc gluconate for prevention of experimental rhinovirus colds. Clin Infect Dis 2001;33:1865-70. PubMed
- Belongia EA, Berg R, Liu K. A randomized trial of zinc nasal spray for the treatment of upper respiratory illness in adults. Am J Med 2001;111:103-8. PubMed
- Mossad SB. Effect of zincum gluconicum nasal gel on the duration and symptom severity of the common cold in otherwise healthy adults. QJM 2003;96:35-43. DOI
- Leitzmann MF, Stampfer MJ, Wu K, et al. Zinc supplement use and risk of prostate cancer. J Natl Cancer Inst 2003;95:1004-7.. PubMed
- Jafek BW, Linschoten M, Murrow BW. Zicam Induced Anosmia. American Rhinologic Society 49th Annual Fall Scientific Meeting abstract. Orlando, Florida. September 20, 2003. http://app.american-rhinologic.org/programs/2003ARSFallProgram071503.pdf (Accessed 24
- Uebayashi H, Hatanaka T, Kanemura F, Tonosaki K. Acute anosmia in the mouse: behavioral discrimination among the four basic taste substances. Physiol Behav 2001;72:291-6.. PubMed
- Barrett S. Zicam Marketers Sued. United States District Court Western District of Michigan Southern Division, Filed October 14, 2003, Case No. 4:03CV0146.
- Bilici M, Yildirim F, Kandil S, et al. Double-blind, placebo-controlled study of zinc sulfate in the treatment of attention deficit hyperactivity disorder. Prog Neuropsychopharmacol Biol Psychiatry 2004;28:181-90.. PubMed
- Polk RE, Healy DP, Sahai J, et al. Effect of ferrous sulfate and multivitamins with zinc on absorption of ciprofloxacin in normal volunteers. Antimicrob Agents Chemother 1989;33:1841-4. PubMed
- Mery C, Delrieu F, Ghozlan R, et al. Controlled trial of D-penicillamine in rheumatoid arthritis. Dose effect and the role of zinc. Scand J Rheumatol 1976;5:241-7. PubMed
- Penttila O, Hurme H, Neuvonen PJ. Effect of zinc sulfate on the absorption of tetracycline and doxycycline in man. Eur J Clin Pharmacol 1975;9:131-4.
- Kondo Y, Yamagata K, Satoh M, et al. Optimal administration schedule of cisplatin for bladder tumor with minimal induction of metallothionein. J Urol 2003;170:2467-70. PubMed
- Doz F, Berens ME, Deschepper CF, et al. Experimental basis for increasing the therapeutic index of cis-diamminedicarboxylatocyclobutaneplatinum(II) in brain tumor therapy by a high-zinc diet. Cancer Chemother Pharmacol 1992;29:219-26.
- Wester PO. Urinary zinc excretion during treatment with different diuretics. Acta Med Scand 1980;208:209-12. PubMed
- Golik A, Modai D, Weissgarten J, et al. Hydrochlorothiazide-amiloride causes excessive urinary zinc excretion. Clin Pharmacol Ther 1987;42:42-4. PubMed
- Leary WP, Reyes AJ, Van der Byl K. Urinary magnesium and zinc excretion after two different single doses of amiloride in healthy adults. Curr Ther Res 1983;34:205-16.
- McBride K, Slotnick B, Margolis FL. Does intranasal application of zinc sulfate produce anosmia in the mouse? An olfactometric and anatomical study. Chem Senses 2003;28:659-70. PubMed
- Burd GD. Morphological study of the effects of intranasal zinc sulfate irrigation on the mouse olfactory epithelium and olfactory bulb. Microsc Res Tech 1993;24:195-213. PubMed
- Ducray A, Bondier JR, Michel G, et al. Recovery following peripheral destruction of olfactory neurons in young and adult mice. Eur J Neurosci 2002;15:1907-17. PubMed
- Mayer AD, Rosenblatt JS. Peripheral olfactory deafferentation of the primary olfactory system in rats using ZnSO4 nasal spray with special reference to maternal behavior. Physiol Behav 1993;53:587-92. PubMed
- DeCook CA, Hirsch AR. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Tisdall FF, Brown A, Defries RD. Persistent anosmia following zinc sulfate nasal spraying. JPed 1938;18:60-2. DOI
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Public Health Advisory. Loss of sense of smell with intranasal cold remedies containing zinc. U.S. Food and Drug Administration, June 16, 2009. Available at: http://www.fda.gov/Drugs/DrugSafety/PublicHealthAdvisories/ucm166059.htm (Accessed 16 June 2009)
- Dooren JC. FDA warns against use of Zicam. The Wall Street Journal, June 16, 2009. Available at: http://online.wsj.com/article/SB124516778692319231.html#mod=djemHL?mg=com-wsj (Accessed 16 June 2009).
- Alexander TH, Davidson TM. Intranasal zinc and anosmia: the zinc-induced anosmia syndrome. Laryngoscope 2006;116:217-20.
- Health Canada / GlaxoSmithKline Consumer Healthcare. Association of long-term, excessive use of zinc-containing Poli-Grip products with myeloneuropathy and blood dyscrasias. February 18, 2010. Available at: http://hc-sc.gc.ca/dhp-mps/alt_formats/pdf/medef
- GlaxoSmithKline Consumer Advisory. GlaxoSmithKline (GSK) warns about a potential health risk associated with long-term, excessive use of GSK's zinc-containing denture adhesives Super Polygrip Original, Ultra Fresh and Extra Care. February 18, 2010. Availa
- Science M, Johnstone J, Roth DE, et al. Zinc for the treatment of the common cold: a systematic review and meta-analysis of randomized controlled trials. CMAJ 2012;184:E551-61. PubMed
- Castilla-Higuero, L., Romero-Gomez, M., Suarez, E., and Castro, M. Acute hepatitis after starting zinc therapy in a patient with presymptomatic Wilson's disease. Hepatology 2000;32(4 Pt 1):877. PubMed
- Sharquie, K. E., Najim, R. A., Farjou, I. B., and Al Timimi, D. J. Oral zinc sulphate in the treatment of acute cutaneous leishmaniasis. Clin.Exp.Dermatol. 2001;26(1):21-26. PubMed
- Dreno, B., Moyse, D., Alirezai, M., Amblard, P., Auffret, N., Beylot, C., Bodokh, I., Chivot, M., Daniel, F., Humbert, P., Meynadier, J., and Poli, F. Multicenter randomized comparative double-blind controlled clinical trial of the safety and efficacy of
- Moore, R. Bleeding gastric erosion after oral zinc sulphate. Br.Med J 3-25-1978;1(6115):754. PubMed
- Jafek, B. W., Linschoten, M. R., and Murrow, B. W. Anosmia after intranasal zinc gluconate use. Am J Rhinol. 2004;18(3):137-141. DOI
- Simonart, T. and de, Maertelaer, V. Systemic treatments for cutaneous warts: a systematic review. J Dermatolog.Treat. 2012;23(1):72-77. PubMed
- Cochran, R. J., Tucker, S. B., and Flannigan, S. A. Topical zinc therapy for acne vulgaris. Int.J Dermatol. 1985;24(3):188-190. DOI
- Morgan, A. A. Bleeding gastric erosion after oral zinc sulphate. Br.Med.J. 5-13-1978;1(6122):1283-1284. PubMed
- Murphy, J. V. Intoxication following ingestion of elemental zinc. JAMA 6-22-1970;212(12):2119-2120.
- Lang, C. J., Rabas-Kolominsky, P., Engelhardt, A., Kobras, G., and Konig, H. J. Fatal deterioration of Wilson's disease after institution of oral zinc therapy. Arch Neurol. 1993;50(10):1007-1008. PubMed
- Fjellner, B. Drug-induced lupus erythematosus aggravated by oral zinc therapy. Acta Derm.Venereol. 1979;59(4):368-370. DOI
- Varas Lorenzo, M. J. Zinc acexamate and ranitidine in the short- and mid-term management of gastroduodenal ulcers. Curr Ther Res 21986;39:19-29.
- Bosch, F. and Jimenez, E. Post-marketing surveillance of zinc acexamate in peptic ulcer treatment. Clin Trials J 1990;27:301-312.
- DeCook, C. A. and Hirsch, A. R. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Crown LA, May JA. Zinc toxicity: denture adhesives, bone marrow failure and polyneuropathy. Tenn Med. 2012 Feb;105(2):39-40, 42.
- Dadamio J, Van Tournout M, Teughels W, Dekeyser C, Coucke W, Quirynen M. Efficacy of different mouthrinse formulations in reducing oral malodour: a randomized clinical trial. J Clin Periodontol. 2013 May;40(5):505-13. PubMed
- Moyle G, Else L, Jackson A, Back D, Yapa MH, Seymour N, Ringner-Nackter L, Karolia Z, Gazzard B, Boffito M. Coadministration of atazanavir-ritonavir and zinc sulfate: impact on hyperbilirubinemia and pharmacokinetics. Antimicrob Agents Chemother. 2013 Aug PubMed
- Zittel S, Ufer F, Gerloff C, Münchau A, Rosenkranz M. Severe myelopathy after denture cream use--is copper deficiency or excess zinc the cause? Clin Neurol Neurosurg. 2014 Jun;121:17-8. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Guidelines for the Use of Antiretroviral Agents in HIV-1-Infected Adults and Adolescents: Drug Interactions between Integrase Inhibitors and Other Drugs. AIDSinfo. July 14, 2016. Available at: https://aidsinfo.nih.gov/guidelines/html/1/adult-and-adolescen
- Ding Y, Jia YY, Li F, et al. The effect of staggered administration of zinc sulfate on the pharmacokinetics of oral cephalexin. Br J Clin Pharmacol. 2012 Mar;73(3):422-7. PubMed
- Fallah R, Sabbaghzadegan S, Karbasi SA, Binesh F. Efficacy of zinc sulfate supplement on febrile seizure recurrence prevention in children with normal serum zinc level: A randomised clinical trial. Nutrition. 2015;31(11-12):1358-61. PubMed
- Lazzerini M, Wanzira H. Oral zinc for treating diarrhoea in children. Cochrane Database Syst Rev. 2016;12:CD005436. PubMed
- Mahmoud AM, Al-Alem U, Dabbous F, et al. Zinc intake and risk of prostate cancer: Case-control study and meta-analysis. PLoS One. 2016;11(11):e0165956. PubMed
- Nagraj SK, George RP, Shetty N, Levenson D, Ferraiolo DM, Shrestha A. Interventions for managing taste disturbances. Cochrane Database Syst Rev. 2017 Dec 20;12(12):CD010470. PubMed
- Yee BE, Richards P, Sui JY, Marsch AF. Serum zinc levels and efficacy of zinc treatment in acne vulgaris: A systematic review and meta-analysis. Dermatol Ther. 2020:e14252. PubMed
- Janyajirawong R, Vilaichone RK, Sethasine S. Efficacy of zinc supplement in minimal hepatic encephalopathy: A prospective, randomized controlled study (Zinc-MHE Trial). Asian Pac J Cancer Prev 2021;22(9):2879-2887. PubMed
- Nakano M, Nakamura Y, Miyazaki A, Takahashi J. Zinc pharmacotherapy for elderly osteoporotic patients with zinc deficiency in a clinical setting. Nutrients 2021;13(6):1814. PubMed
- Tolino E, Skroza N, Mambrin A, et al. An open-label study comparing oral zinc to lymecycline in the treatment of acne vulgaris. J Clin Aesthet Dermatol 2021;14(5):56-58.
- Hunter J, Arentz S, Goldenberg J, et al. Zinc for the prevention or treatment of acute viral respiratory tract infections in adults: a rapid systematic review and meta-analysis of randomised controlled trials. BMJ Open. 2021;11(11):e047474. PubMed
- Yamazaki K, Kageyama H, Fujiyama T, Ito T, Urano S, Honda T. A case of systemic contact dermatitis due to zinc supplements. Int J Dermatol 2022. PubMed
- Magham K, Han J, Eilbert W, Bunney EB. Severe copper deficiency anemia caused by zinc supplement use. Am J Emerg Med 2023;72:222. PubMed
- Sivakumar RR, Chinnaiah Govindareddy D, Sahoo J, Bobby Z, Chinnakali P. Effect of daily zinc supplementation for 12 weeks on serum thyroid auto-antibody levels in children and adolescents with autoimmune thyroiditis - a randomized controlled trial. J Pedi PubMed
- AlDhasee O, AlMalki H, AlKharashi N, AlJeraisy N, Al Deeb M. Acute zinc sulfate overdose: clinical presentation and management. BMJ Case Rep 2025;18(1):e263899. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Quercetin 26 references
- Shoskes DA, Zeitlin SI, Shahed A, Rajfer J. Quercetin in men with category III chronic prostatitis: A preliminary prospective, double-blind, placebo-controlled trial. Urol 1999;54:960-3. PubMed
- Starvic B. Quercetin in our diet: from potent mutagen to probable anticarcinogen. Clin Biochem 1994;27:245-8. PubMed
- Ferry DR, Smith A, Malkhandi J, et al. Phase I clinical trial of the flavonoid quercetin: Pharmacokinetics and evidence for in vivo tyrosine kinase inhibition. Clin Cancer Res 1996;2:659-67..
- Obach RS. Inhibition of human cytochrome P450 enzymes by constituents of St. John's wort, an herbal preparation used in the treatment of depression. J Pharmacol Exp Ther 2000;294:88-95. DOI
- Edwards RL, Lyon T, Litwin SE, et al. Quercetin reduces blood pressure in hypertensive subjects. J Nutr 2007;137:2405-11.
- Kim KA, Park PW, Kim HK, et al. Effect of quercetin on the pharmacokinetics of rosiglitazone, a CYP2C8 substrate, in healthy subjects. J Clin Pharmacol 2005;45:941-6. PubMed
- DiCenzo R, Frerichs V, Larppanichpoonphol P, et al. Effect of quercetin on the plasma and intracellular concentrations of saquinavir in healthy adults. Pharmacotherapy 2006;26:1255-61. PubMed
- Choi JS, Choi BC, Choi KE. Effect of quercetin on the pharmacokinetics of oral cyclosporine. Am J Health Syst Pharm 2004;61:2406-9. PubMed
- Choi JS, Jo BW, Kim YC. Enhanced paclitaxel bioavailability after oral administration of paclitaxel or prodrug to rats pretreated with quercetin. Eur J Pharm Biopharm 2004;57:313-8. PubMed
- Vaclavikova R, Horsky S, Simek P, Gut I. Paclitaxel metabolism in rat and human liver microsomes is inhibited by phenolic antioxidants. Naunyn Schmiedebergs Arch Pharmacol 2003;368:200-9. PubMed
- Di Bari L, Ripoli S, Pradhan S, Salvadori P. Interactions between quercetin and warfarin for albumin binding: A new eye on food/drug interference. Chirality 2010;22:593-6. PubMed
- Lamson, D. W. and Brignall, M. S. Antioxidants and cancer, part 3: quercetin. Altern.Med.Rev. 2000;5(3):196-208.
- Duan KM, Wang SY, Ouyang W, Mao YM, Yang LJ. Effect of quercetin on CYP3A activity in Chinese healthy participants. J Clin Pharmacol 2012;52(6):940-6. PubMed
- Wang SY, Duan KM, Li Y, et al. Effect of quercetin on P-glycoprotein transport ability in Chinese healthy subjects. Eur J Clin Nutr 2013;67(4):390-4. PubMed
- Nguyen MA, Staubach P, Wolffram S, Langguth P. Effect of single-dose and short-term administration of quercetin on the pharmacokinetics of talinolol in humans - Implications for the evaluation of transporter-mediated flavonoid-drug interactions. Eur J Pha PubMed
- Wu LX, Guo CX, Chen WQ, et al. Inhibition of the organic anion-transporting polypeptide 1B1 by quercetin: an in vitro and in vivo assessment. Br J Clin Pharmacol 2012;73(5):750-7.
- Ahrens MJ, Thompson DL. Effect of emulin on blood glucose in type 2 diabetics. J Med Food. 2013;16(3):211-5. PubMed
- Larson A, Witman MA, Guo Y, et al. Acute, quercetin-induced reductions in blood pressure in hypertensive individuals are not secondary to lower plasma angiotensin-converting enzyme activity or endothelin-1: nitric oxide. Nutr Res. 2012;32(8):557-64. PubMed
- Bedada SK, Neerati P. Evaluation of the effect of quercetin treatment on CYP2C9 enzyme activity of diclofenac in healthy human volunteers. Phytother Res. 2018 Feb;32(2):305-311. doi: 10.1002/ptr.5978. PubMed
- Zhao Q, Wei J, Zhang H. Effects of quercetin on the pharmacokinetics of losartan and its metabolite EXP3174 in rats. Xenobiotica 2019;49(5):563-8. PubMed
- Bhutani P, Rajanna PK, Paul AT. Impact of quercetin on pharmacokinetics of quetiapine: insights from in-vivo studies in wistar rats. Xenobiotica. 2020:1-7.
- Li C, Wang X, Bi Y, et al. Potent Inhibitors of Organic Anion Transporters 1 and 3 From Natural Compounds and Their Protective Effect on Aristolochic Acid Nephropathy. Toxicol Sci. 2020;175(2):279-291. PubMed
- Ni Y, Duan Z, Zhou D, et al. Identification of Structural Features for the Inhibition of OAT3-Mediated Uptake of Enalaprilat by Selected Drugs and Flavonoids. Front Pharmacol. 2020;11:802. PubMed
- Song YK, Yoon JH, Woo JK, et al. Quercetin is a flavonoid breast cancer resistance protein inhibitor with an impact on the oral pharmacokinetics of sulfasalazine in rats. Pharmaceutics 2020;12(5):397. PubMed
- Ahmad E, Jahangir M, Ismail MA, et al. Influence of quercetin pretreatment on pharmacokinetics of warfarin in rats. Curr Drug Saf 2022. PubMed
- Nambiar A, Kellogg D 3rd, Justice J, et al. Senolytics dasatinib and quercetin in idiopathic pulmonary fibrosis: results of a phase I, single-blind, single-center, randomized, placebo-controlled pilot trial on feasibility and tolerability. EBioMedicine 20 PubMed
Chrysin 23 references
- Galijatovic A, Otake Y, Walle UK, Walle T. Extensive metabolism of the flavonoid chrysin by human Caco-2 and Hep G2 cells. Xenobiotica 1999;29:1241-56. PubMed
- Lee H, Yeom H, Kim YG, et al. Structure-related inhibition of human hepatic caffeine N3-demethylation by naturally occurring flavonoids. Biochem Pharmacol 1998;55:1369-75. PubMed
- Galijatovic A, Walle UK, Walle T. Induction of UDP-glucuronosyltransferase by the flavonoids chrysin and quercetin in Caco-2 cells. Pharm Res 2000;17:21-6.
- Walle UK, Galijatovic A, Walle T. Transport of the flavonoid chrysin and its conjugated metabolites by the human intestinal cell line Caco-2. Biochem Pharmacol 1999;58:431-8. PubMed
- Kao YC, Zhou C, Sherman M, et al. Molecular basis of the inhibition of human aromatase (estrogen synthetase) by flavone and isoflavone phytoestrogens: A site-directed mutagenesis study. Environ Health Perspect 1998;106:85-92. PubMed
- Jeong HJ, Shin YG, Kim IH, Pezzuto JM. Inhibition of aromatase activity by flavonoids. Arch Pharm Res 1999;22:309-12. PubMed
- Walle T, Otake Y, Galijatovic A, et al. Induction of UDP-glucuronosyltransferase UGT1A1 by the flavonoid chrysin in the human hepatoma cell line hep G2. Drug Metab Dispos 2000;28:1077-82. DOI
- Walle T, Otake Y, Brubaker JA, et al. Disposition and metabolism of the flavonoid chrysin in normal volunteers. Br J Clin Pharmacol 2001;51:143-6. DOI
- Galijatovic A, Otake Y, Walle UK, Walle T. Induction of UDP-glucuronosyltransferase UGT1A1 by the flavonoid chrysin in Caco-2 cells--potential role in carcinogen bioinactivation. Pharm Res 2001;18:374-9. PubMed
- Lautraite S, Musonda AC, Doehmer J, et al. Flavonoids inhibit genetic toxicity produced by carcinogens in cells expressing CYP1A2 and CYP1A1. Mutagenesis 2002;17:45-53. PubMed
- Han, D. H., Denison, M. S., Tachibana, H., and Yamada, K. Relationship between estrogen receptor-binding and estrogenic activities of environmental estrogens and suppression by flavonoids. Biosci.Biotechnol.Biochem 2002;66(7):1479-1487. PubMed
- O'Leary, K. A., de Pascual-Tereasa, S., Needs, P. W., Bao, Y. P., O'Brien, N. M., and Williamson, G. Effect of flavonoids and vitamin E on cyclooxygenase-2 (COX-2) transcription. Mutat.Res 7-13-2004;551(1-2):245-254. PubMed
- Woodman, O. L. and Chan, E. C. Vascular and anti-oxidant actions of flavonols and flavones. Clin Exp Pharmacol Physiol 2004;31(11):786-790. PubMed
- Simons, A. L., Renouf, M., Hendrich, S., and Murphy, P. A. Human gut microbial degradation of flavonoids: structure-function relationships. J Agric.Food Chem 5-18-2005;53(10):4258-4263. PubMed
- Kim, H. J., Lee, S. B., Park, S. K., Kim, H. M., Park, Y. I., and Dong, M. S. Effects of hydroxyl group numbers on the B-ring of 5,7-dihydroxyflavones on the differential inhibition of human CYP 1A and CYP1B1 enzymes. Arch Pharm Res 2005;28(10):1114-1121 PubMed
- Moon, Y. J., Wang, X., and Morris, M. E. Dietary flavonoids: effects on xenobiotic and carcinogen metabolism. Toxicol In Vitro 2006;20(2):187-210. PubMed
- Landolfi, R., Mower, R. L., and Steiner, M. Modification of platelet function and arachidonic acid metabolism by bioflavonoids. Structure-activity relations. Biochem Pharmacol 5-1-1984;33(9):1525-1530. PubMed
- Tsyrlov, I. B., Mikhailenko, V. M., and Gelboin, H. V. Isozyme- and species-specific susceptibility of cDNA-expressed CYP1A P-450s to different flavonoids. Biochim.Biophys Acta 4-13-1994;1205(2):325-335. PubMed
- Collins, B. M., McLachlan, J. A., and Arnold, S. F. The estrogenic and antiestrogenic activities of phytochemicals with the human estrogen receptor expressed in yeast. Steroids 1997;62(4):365-372. PubMed
- Kuiper, G. G., Lemmen, J. G., Carlsson, B., Corton, J. C., Safe, S. H., van der Saag, P. T., van der Burg, B., and Gustafsson, J. A. Interaction of estrogenic chemicals and phytoestrogens with estrogen receptor beta. Endocrinology 1998;139(10):4252-4263. PubMed
- Liu G, Xie W, He AD, et al. Antiplatelet activity of chrysin via inhibiting platelet aIIbß3-mediated signaling pathway. Mol Nutr Food Res 2016;60(9):1984-93.
- Noh K, Oh do G, Nepal MR, et al. Pharmacokinetic interaction of chrysin with caffeine in rats. Biomol Ther (Seoul) 2016;24(4):446-52. PubMed
- Mohos V, Fliszár-Nyúl E, Ungvári O, et al. Effects of Chrysin and Its Major Conjugated Metabolites Chrysin-7-Sulfate and Chrysin-7-Glucuronide on Cytochrome P450 Enzymes and on OATP, P-gp, BCRP, and MRP2 Transporters. Drug Metab Dispos 2020;48(10):1064-10 PubMed
Diindolylmethane 14 references
- Natl Inst Health, Natl Inst Environmental Health Sci. Indole-3-carbinol. Available at: http://ntp-server.niehs.nih.gov.
- Balk JL. Indole-3-carbinol for cancer prevention. Altern Med Alert 2000; 3:105-7.
- Riby JE, Chang GHF, Firestone GL, Bjeldanes LF. Ligand-independent activation of estrogen receptor function by 3,3'-diindolylmethane in human breast cancer cells. Biochem Pharmacol 2000;60:167-77. PubMed
- Lake BG, Tredger JM, Renwick AB, et al. 3'3-diindolylmethane induces CYP1A2 in cultured precision-cut human liver slices. Xenobiotica 1998;28:803-11. PubMed
- Dalessandri, K. M., Firestone, G. L., Fitch, M. D., Bradlow, H. L., and Bjeldanes, L. F. Pilot study: effect of 3,3'-diindolylmethane supplements on urinary hormone metabolites in postmenopausal women with a history of early-stage breast cancer. Nutr Canc PubMed
- Reed, G. A., Arneson, D. W., Putnam, W. C., Smith, H. J., Gray, J. C., Sullivan, D. K., Mayo, M. S., Crowell, J. A., and Hurwitz, A. Single-dose and multiple-dose administration of indole-3-carbinol to women: pharmacokinetics based on 3,3'-diindolylmetha
- Reed, G. A., Sunega, J. M., Sullivan, D. K., Gray, J. C., Mayo, M. S., Crowell, J. A., and Hurwitz, A. Single-dose pharmacokinetics and tolerability of absorption-enhanced 3,3'-diindolylmethane in healthy subjects. Cancer Epidemiol.Biomarkers Prev. 2008; PubMed
- Del Priore G., Gudipudi, D. K., Montemarano, N., Restivo, A. M., Malanowska-Stega, J., and Arslan, A. A. Oral diindolylmethane (DIM): pilot evaluation of a nonsurgical treatment for cervical dysplasia. Gynecol.Oncol. 2010;116(3):464-467. PubMed
- Heath, E. I., Heilbrun, L. K., Li, J., Vaishampayan, U., Harper, F., Pemberton, P., and Sarkar, F. H. A phase I dose-escalation study of oral BR-DIM (BioResponse 3,3'- Diindolylmethane) in castrate-resistant, non-metastatic prostate cancer. Am.J.Transl.R
- Jellinck, P. H., Forkert, P. G., Riddick, D. S., Okey, A. B., Michnovicz, J. J., and Bradlow, H. L. Ah receptor binding properties of indole carbinols and induction of hepatic estradiol hydroxylation. Biochem.Pharmacol. 3-9-1993;45(5):1129-1136. PubMed
- Bui PV, Moualla M, Upson DJ. A Possible Association of Diindolylmethane with Pulmonary Embolism and Deep Venous Thrombosis. Case Rep Med. 2016;2016:7527098. PubMed
- Castañon A, Tristram A, Mesher D, Powell N, Beer H, Ashman S, Rieck G, Fielder H, Fiander A, Sasieni P. Effect of diindolylmethane supplementation on low-grade cervical cytological abnormalities: double-blind, randomised, controlled trial. Br J Cancer. 20 PubMed
- Le TM, Sanders CJ, van de Corput L, van Erpecum KJ, Röckmann H. Drug rash with eosinophilia and systemic symptoms caused by the dietary supplement diindolylmethane. J Allergy Clin Immunol Pract. 2016 Jan-Feb;4(1):175-6. PubMed
- Pence ST, Mehta K, Crum-Bailey J. The Serious Side of Supplements: An Ischemic Stroke in a Healthy 38-year-old Female. Mil Med 2022. PubMed
Agaricus Mushroom 5 references
- Hsu CH, Liao YL, Lin SC, et al. The mushroom Agaricus Blazei Murill in combination with metformin and gliclazide improves insulin resistance in type 2 diabetes: a randomized, double-blinded, and placebo-controlled clinical trial. J Altern Complement Med 2
- Mukai H, Watanabe T, Ando M, Katsumata N. An alternative medicine, Agaricus blazei, may have induced severe hepatic dysfunction in cancer patients. Jpn J Clin Oncol 2006;36:808-10. PubMed
- Ohno S, Sumiyoshi Y, Hashine K, et al. Phase I clinical study of the dietary supplement, Agaricus blazei Murill, in cancer patients in remission. Evid Based Complement Alternat Med 2011, doi 10.1155/2011/192381.
- Suehiro M, Katoh N, Kishimoto S. Chelitis due to Agaricus blazei Murill mushroom extract. Contact Dermatitis 2007;56(5):293-4.
- Iwai N, Okuda T, Sawada R, et al. Interstitial lung disease associated with Agaricus blazei Murill in a patient with pancreatic ductal adenocarcinoma receiving gemcitabine-based therapy. Case Rep Gastroenterol 2022;16(1):229-234.
Red Clover 24 references
- Kurzer MS, Xu X. Dietary phytoestrogens. Annu Rev Nutr 1997;17:353-81. PubMed
- Electronic Code of Federal Regulations. Title 21. Part 182 -- Substances Generally Recognized As Safe. Available at: https://www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfcfr/CFRSearch.cfm?CFRPart=182
- Budzinski JW, Foster BC, Vandenhoek S, Arnason JT. An in vitro evaluation of human cytochrome P450 3A4 inhibition by selected commercial herbal extracts and tinctures. Phytomedicine 2000;7:273-82. PubMed
- This P, De La Rochefordiere A, Clough K, et al. Phytoestrogens after breast cancer. Endocr Relat Cancer 2001;8:129-34. PubMed
- Tice J, Cummings SR, Ettinger B, et al. Few adverse effects of two red clover extracts rich in phytoestrogens: a multicenter, placebo-controlled trial. Alt Ther 2001;7:S33.
- Ingram DM, Hickling C, West L, et al. A double-blind randomized controlled trial of isoflavones in the treatment of cyclical mastalgia. The Breast 2002;11:170-4. PubMed
- Unger M, Frank A. Simultaneous determination of the inhibitory potency of herbal extracts on the activity of six major cytochrome P450 enzymes using liquid chromatography/mass spectrometry and automated online extraction. Rapid Commun Mass Spectrom 2004;1 PubMed
- Cheong JL, Bucknall R. Retinal vein thrombosis associated with a herbal phytoestrogen preparation in a susceptible patient. Postgrad Med J 2005;81:266-7.. PubMed
- Geller SE, Shulman LP, van Breemen RB, et al. Safety and efficacy of black cohosh and red clover for the management of vasomotor symptoms: a randomized controlled trial. Menopause 2009;16:1156-66. PubMed
- Hidalgo LA, Chedraui PA, Morocho N, et al. The effect of red clover isoflavones on menopausal symptoms, lipids and vaginal cytology in menopausal women: a randomized, double-blind, placebo-controlled study. Gynecol Endocrinol 2005;21(5):257-264. PubMed
- Campbell MJ, Woodside JV, Honour JW, et al. Effect of red clover-derived isoflavone supplementation on insulin-like growth factor, lipid and antioxidant status in healthy female volunteers: a pilot study. Eur J Clin Nutr 2004;58(1):173-179. PubMed
- Guerrero JA, Lozano ML, Castillo J, et al. Flavonoids inhibit platelet function through binding to the thromboxane A2 receptor. J Thromb Haemost 2005;3(2):369-376. PubMed
- Kondo K, Suzuki Y, Ikeda Y, Umemura K. Genistein, an isoflavone included in soy, inhibits thrombotic vessel occlusion in the mouse femoral artery and in vitro platelet aggregation. Eur J Pharmacol 2002;455(1):53-57. PubMed
- Polini N, Rauschemberger MB, Mendiberri J, et al. Effect of genistein and raloxifene on vascular dependent platelet aggregation. Mol Cell Endocrinol 2007;267(1-2):55-62. PubMed
- Wuttke W, Jarry H, Seidlova-Wuttke D. Plant-derived alternative treatments for the aging male: facts and myths. Aging Male 2010;13(2):75-81. PubMed
- Villaseca P. Non-estrogen conventional and phytochemical treatments for vasomotor symptoms: what needs to be known for practice. Climacteric 2012;15(2):115-124. PubMed
- Chen, Y., Xiao, C. Q., He, Y. J., Chen, B. L., Wang, G., Zhou, G., Zhang, W., Tan, Z. R., Cao, S., Wang, L. P., and Zhou, H. H. Genistein alters caffeine exposure in healthy female volunteers. Eur.J Clin.Pharmacol. 2011;67(4):347-353. PubMed
- Friedman, J. A., Taylor, S. A., McDermott, W., and Alikhani, P. Multifocal and recurrent subarachnoid hemorrhage due to an herbal supplement containing natural coumarins. Neurocrit.Care 2007;7(1):76-80. PubMed
- Hooper, L., Madhavan, G., Tice, J. A., Leinster, S. J., and Cassidy, A. Effects of isoflavones on breast density in pre- and post-menopausal women: a systematic review and meta-analysis of randomized controlled trials. Hum.Reprod.Update. 2010;16(6):745-7 PubMed
- Orr A and Parker R. Red clover causing symptoms suggestive of methotrexate toxicity in a patient on high-dose methotrexate. Menopause Int. 2013;19(3):133-134. PubMed
- Clifton-Bligh PB, et al. Red cover isoflavones enriched with formononetin lower serum LDL cholesterol- a randomized, double-blind, placebo-controlled trial. Eur J Clin Nutr. 2015;69(1):134-142.
- Risk assessment for peri- and post-menopausal women taking food supplements containing isolated isoflavones. EFSA Panel on Food Additives and Nutrient Sources added to Food (ANS). 2015. DOI
- Ferraris C, Ballestra B, Listorti C, et al. Red clover and lifestyle changes to contrast menopausal symptoms in premenopausal patients with hormone-sensitive breast cancer receiving tamoxifen. Breast Cancer Res Treat 2020;180(1):157-65. doi: 10.1007/s1054 PubMed
- Chen L, Choi J, Leonard SW, et al. No Clinically Relevant Pharmacokinetic Interactions of a Red Clover Dietary Supplement with Cytochrome P450 Enzymes in Women. J Agric Food Chem. 2020;68(47):13929-13939. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC