
Night Time Superfoods Hot Cocoa Ingredients & Drug Interactions
by moonbrew
What is this page for?
First and foremost: checking Night Time Superfoods Hot Cocoa against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Night Time Superfoods Hot Cocoa is a dietary supplement by moonbrew with 10 active ingredients. Its ingredients are commonly taken for replacing fluids and electrolytes, preventing dehydration during exercise or illness, treating low blood sodium (under medical care).Based on those ingredients, 2,251 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Dietary Fiber, L-Theanine, L-Tryptophan. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Night Time Superfoods Hot Cocoa by moonbrew
Ask about any prescription or over-the-counter medication and we check it for interactions with Night Time Superfoods Hot Cocoa by moonbrew — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Night Time Superfoods Hot Cocoa by moonbrew
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
Night Time Superfoods Hot Cocoa is a 13-ingredient powder blend centered on sleep and relaxation support. The active ingredients include sodium, potassium, iron, and zinc (minerals linked to various health roles, from blood pressure regulation to immune function); L-tryptophan and L-theanine (amino acids traditionally used to promote calm and sleep); Magnesium (a mineral involved in muscle relaxation and nervous system function); and botanical extracts—Chamomile flower, Reishi Fruiting Body, Polygala root, Jujube seed, Silk Tree bark, and Arborvitae seed—each with historical use in sleep and stress support.
The product also contains inactive ingredients: cocoa flavoring, citric acid, monk fruit extract, and sea salt.
Does it work?
Not established
The evidence for most ingredients in this product is limited. Magnesium is Effective for constipation and dyspepsia, and Likely Effective for pre-eclampsia; it is also Effective for low magnesium levels.
Iron is Effective for iron deficiency anemia and chronic disease-related anemia. Zinc is Effective for zinc deficiency and Likely Effective for Wilson disease.
L-theanine is Possibly Effective for cognitive function, but evidence for sleep or anxiety is rated Insufficient. L-tryptophan is rated Possibly Ineffective for depression, and evidence for other uses (anxiety, sleep quality) is Insufficient.
Sodium, potassium, and the botanical extracts (chamomile, reishi, polygala, jujube, silk tree, arborvitae) have no effectiveness ratings in our data, meaning either they have not been well studied for their claimed uses or the evidence is not established. The product's overall sleep support claim is not backed by strong evidence for most of its components.
How safe is it?
Well-documented data
Most ingredients are generally well tolerated at recommended amounts. Sodium and potassium are essential in normal food amounts, but excess can be harmful—sodium is linked to high blood pressure and heart strain, while high potassium can cause dangerous blood levels, especially in those with kidney disease.
Iron, zinc, magnesium, and L-theanine are well tolerated at typical doses but can cause gastrointestinal side effects (nausea, diarrhea, abdominal discomfort) in some people. L-tryptophan has a historical safety concern: in the late 1980s, a contaminated batch from one manufacturer caused eosinophilia-myalgia syndrome, a serious neurological disorder; modern products are safer, but the risk exists.
Chamomile flower, Reishi, Polygala root, and Jujube seed have limited human safety data. Arborvitae seed extract contains thujone, which at high doses or with long-term use may cause dizziness, tremors, vomiting, and kidney damage.
For pregnancy and breastfeeding, safety varies by ingredient: magnesium and iron are generally considered safe in pregnancy under medical guidance, but L-tryptophan is rated Possibly Unsafe in pregnancy and Likely Unsafe while breastfeeding; L-theanine, Albizia, and Arborvitae lack sufficient data and are best avoided. Check with your doctor before use if you are pregnant or nursing.
Meds to double-check
Major interaction found
Before you take this product, double-check your exact medications against these drug types. Most serious: if you take levodopa/carbidopa (Parkinson's), CNS depressants (sleeping pills, sedatives, alcohol), serotonergic drugs (antidepressants, SNRI/SSRI), or blood pressure medications—especially ACE inhibitors, ARBs, calcium channel blockers, or potassium-sparing diuretics.
Also watch for quinolone or tetracycline antibiotics, bisphosphonates, thyroid medication, skeletal muscle relaxants, blood sugar drugs, antiretroviral HIV medications, lithium, corticosteroids, and any sodium-containing supplements or drugs. No interactions are documented for the chamomile, reishi, polygala, jujube, or one of the blends because we could not check them.
The bottom line
Scorecard at a glanceFully disclosed formula with no established evidence rating for its marketed use. Major medication interactions have been identified, and safety information is well characterized.
This product is designed for evening relaxation and sleep, combining minerals, amino acids, and botanicals with limited or mixed evidence. If you take blood pressure medications, blood thinners, thyroid drugs, Parkinson's medication, or any psychiatric medication, talk to your pharmacist before starting—the interactions are real and could affect how your drugs work.
Even if you have no prescriptions, the sedating ingredients may make you drowsy, so avoid this before driving. Pregnant or breastfeeding?
Check with your doctor first.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 13 of 14 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Mar 25, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Night Time Superfoods Hot Cocoa, straight from the product label.
| Brand | moonbrew |
|---|---|
| Net contents | 5.95 Ounce(s); 168 Gram(s) |
| Market status | On market |
| Date entered into DSLD | Mar 25, 2025 |
| DSLD ID | 328209 |
| Product type | Other Combinations |
| Supplement form | Powder |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Vegan, Vegetarian, Adult (18 - 50 Years), Gluten Free, Dairy Free, Sugar Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
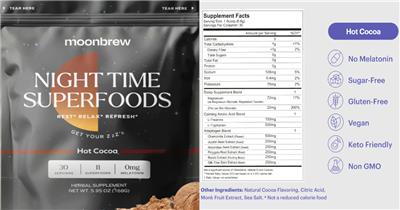
Supplement Facts
The label details for Night Time Superfoods Hot Cocoa by moonbrew, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Calories | 5 Calorie(s) | -- |
| Total Carbohydrates | 1 Gram(s) | 1% |
| Sodium | 126 mg | 5% |
| Potassium | 75 mg | 2% |
| Iron | 0.4 mg | 2% |
| L-Tryptophan | 500 mg | -- |
| Total Sugars | 0 Gram(s) | -- |
| Total Fat | 0 Gram(s) | -- |
| Dietary Fiber | 1 Gram(s) | 2% |
| Protein | 0 Gram(s) | -- |
| Chamomile flower extract | 500 mg | -- |
| L-Theanine | 150 mg | -- |
| Zinc | 22 mg | 200% |
| Reishi Fruiting Body Extract | 250 mg | -- |
| Polygala root extract | 250 mg | -- |
| Jujube seed extract | 250 mg | -- |
| Silk Tree bark extract | 250 mg | -- |
| Adaptogen Blend | 0 NP | -- |
| Sleep Supplement Blend | 0 NP | -- |
| Magnesium | 72 mg | 17% |
| Calming Amino Acid Blend | 0 NP | -- |
| Arborvitae Seed Extract | 250 mg | -- |
Other ingredients: Cocoa Flavoring, Natural, Citric Acid, Monk Fruit Extract, Sea Salt
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formulation
Not a significant source of Cholesterol, Vitamin D, and Calcium.
Rest Relax Refresh Get your zzz's
0 mg melatonin
No melatonin Sugar-free Gluten-free Non GMO
Vegan
Precautions
Not a reduced calorie food
General Statements
Tear here
Formula
11 superfoods
Keto friendly
FDA Statement of Identity
Herbal Supplement
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Night Time Superfoods Hot Cocoa by moonbrew label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Night Time Superfoods Hot Cocoa by moonbrew
These are the 10 active ingredients this product is made of. Select any to open its full monograph.
Serving size5.6 Gram(s) Dosage formPowder Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Sodium
Interacts with205 drugs
Sodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets g...
Sodium monograph & interactionsPotassium
Interacts with62 drugs
Potassium is an essential mineral your body needs for nerve signals, muscle function, and a steady heartbeat, and most people get enough from a balanc...
Potassium monograph & interactionsIron
Interacts with80 drugs
Iron is an essential mineral your body needs to make hemoglobin and carry oxygen in the blood. Supplements are mainly useful for treating or preventin...
Iron monograph & interactionsDietary Fiber
Interacts with2,025 drugs
Black psyllium is a soluble-fiber supplement made from the seeds of a Plantago plant, used mostly to ease constipation and support digestive health. I...
Dietary Fiber monograph & interactionsProtein
Adaptogen Blend
Interacts with327 drugs
Jiaogulan is a climbing vine used in traditional Chinese medicine as an adaptogen and for heart, blood sugar, and cholesterol support. Early human and...
Adaptogen Blend monograph & interactions- › Chamomile flower extract
- › Reishi Fruiting Body Extract
- › Polygala root extract
- › Jujube seed extract
- › Silk Tree bark extract
- › Arborvitae Seed Extract
Calming Amino Acid Blend
Other (inactive) ingredients: Cocoa Flavoring, Natural, Citric Acid, Monk Fruit Extract, Sea Salt. These complete the product’s ingredient list but are not active constituents.
Night Time Superfoods Hot Cocoa by moonbrew Drug Interactions
HelloPharmacist Interaction Report
Night Time Superfoods Hot Cocoa by moonbrew contains several ingredients with documented interactions.
The most serious is L-tryptophan, which can cause additive sedative effects when combined with CNS depressants (sedatives, sleep aids, alcohol, and similar drugs) — this is a Major-severity interaction. L-tryptophan may also increase serotonergic effects when paired with antidepressants and other serotonergic drugs, raising the theoretical risk of serotonin syndrome.
Read the full breakdown — every affected drug type, severity by severity
Magnesium carries a Major interaction with levodopa/carbidopa (Parkinson's medication), reducing its effectiveness by up to 35%. Magnesium also has Moderate interactions with skeletal muscle relaxants, calcium channel blockers, quinolone antibiotics, bisphosphonates, and blood sugar medications (sulfonylureas).
Sodium and potassium together create Moderate risks: sodium may reduce the effect of blood pressure drugs and interact with lithium and corticosteroids, while potassium can cause dangerously high blood levels when combined with ACE inhibitors, ARBs, or potassium-sparing diuretics.
Iron has Moderate interactions with several antibiotics (quinolones and tetracyclines), thyroid medication (levothyroxine), and other drugs—spacing doses by 2–4 hours usually helps. Zinc similarly reduces absorption of certain antibiotics and HIV medications.
L-theanine may lower blood pressure and theoretically add to CNS depressant effects. Albizia (Silk Tree bark) may potentiate CNS depressants.
Altogether, these interactions span 850 individual medications.
Chamomile flower extract, Reishi, Polygala root, and Jujube seed extract could not be checked—we hold no interaction data for them. Please use the medication checker below with your exact prescriptions before you start.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Night Time Superfoods Hot Cocoa?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Night Time Superfoods Hot Cocoa interact with 2,251 drugs. Click any drug to see the details.
9 of the 10 ingredients in Night Time Superfoods Hot Cocoa interact with drugs. Each result below shows which ingredient is responsible. Dietary Fiber L-Theanine L-Tryptophan Adaptogen Blend Magnesium Sodium Iron Zinc Potassium
AcepromazineAtravet
How Acepromazine interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acepromazine interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acepromazine interactionChamomile Flower ExtractCns Depressants Moderate
Interaction Summary
Theoretically, German chamomile might have additive effects when used with CNS depressants.
Read the full Chamomile Flower Extract + Acepromazine interactionJujube Seed ExtractCns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might cause additive sedative effects when taken with CNS depressants.
Read the full Jujube Seed Extract + Acepromazine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acepromazine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acepromazine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Butalbital, Caffeine, Codeine interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionChamomile Flower ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +2 Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP3A4 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Butalbital, Caffeine, Codeine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Butalbital, Codeine interactionChamomile Flower ExtractCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, German chamomile might have additive effects when used with CNS depressants.
Read the full Chamomile Flower Extract + Acetaminophen, Butalbital, Codeine interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Butalbital, Codeine interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Butalbital, Codeine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Butalbital, Codeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Butalbital, Codeine Phosphate interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionChamomile Flower ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP2D6 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionJujube Seed ExtractCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, zizyphus might cause additive sedative effects when taken with CNS depressants.
Read the full Jujube Seed Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Butalbital, Codeine Phosphate interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionChamomile Flower ExtractCns Depressants, Cytochrome P450 3a4 (cyp3a4) Substrates +2 Moderate
Interaction Summary
Theoretically, German chamomile might have additive effects when used with CNS depressants.
Read the full Chamomile Flower Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Caffeine, Codeine interactionChamomile Flower ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cns Depressants +2 Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP2D6 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Caffeine, Codeine interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Caffeine, Codeine interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Caffeine, Codeine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Caffeine, Codeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Caffeine, Codeine, Salicylamide interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionChamomile Flower ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +2 Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP3A4 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionJujube Seed ExtractCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, zizyphus might cause additive sedative effects when taken with CNS depressants.
Read the full Jujube Seed Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Caffeine, Codeine, Salicylamide interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Caffeine, Dihydrocodeine interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionChamomile Flower ExtractCns Depressants, Cytochrome P450 3a4 (cyp3a4) Substrates +2 Moderate
Interaction Summary
Theoretically, German chamomile might have additive effects when used with CNS depressants.
Read the full Chamomile Flower Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Dihydrocodeine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants, Serotonergic Drugs Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionChamomile Flower ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +2 Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP2D6 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionL-theanineSerotonergic Drugs, Cns Depressants Minor
Interaction Summary
Clinical studies regarding the effects of L-theanine on serotonin levels are conflicting.
Read the full L-theanine + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionAcetaminophen, Chlorpheniramine, Phenylpropanolamine, OpiumHista-Derfule
How Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanSerotonergic Drugs, Cns Depressants Major
Interaction Summary
Theoretically, combining L-tryptophan with serotonergic drugs might cause additive serotonergic effects.
Read the full L-tryptophan + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionChamomile Flower ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP3A4 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionL-theanineSerotonergic Drugs, Cns Depressants Minor
Interaction Summary
Clinical studies regarding the effects of L-theanine on serotonin levels are conflicting.
Read the full L-theanine + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionAcetaminophen, Chlorzoxazone, CodeineAcetazone Forte C8, Parafon Forte C8
How Acetaminophen, Chlorzoxazone, Codeine interacts with Night Time Superfoods Hot Cocoa — through 7 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Chlorzoxazone, Codeine interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Chlorzoxazone, Codeine interactionChamomile Flower ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants +1 Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP1A2 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Chlorzoxazone, Codeine interactionMagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Acetaminophen, Chlorzoxazone, Codeine interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Chlorzoxazone, Codeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorzoxazone, Codeine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Chlorzoxazone, Codeine interactionAcetaminophen, CodeineTylenol No.3, Tylenol w/ Codeine
How Acetaminophen, Codeine interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Codeine interactionChamomile Flower ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP2D6 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Codeine interactionJujube Seed ExtractCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, zizyphus might cause additive sedative effects when taken with CNS depressants.
Read the full Jujube Seed Extract + Acetaminophen, Codeine interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Codeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Codeine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Codeine interactionAcetaminophen, Codeine, DoxylamineMersyndol
How Acetaminophen, Codeine, Doxylamine interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Codeine, Doxylamine interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Codeine, Doxylamine interactionChamomile Flower ExtractCns Depressants, Cytochrome P450 2d6 (cyp2d6) Substrates +1 Moderate
Interaction Summary
Theoretically, German chamomile might have additive effects when used with CNS depressants.
Read the full Chamomile Flower Extract + Acetaminophen, Codeine, Doxylamine interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Codeine, Doxylamine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Codeine, Doxylamine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Codeine, Doxylamine interactionAcetaminophen, Codeine, MethocarbamolAcetaminophen, Codeine, Methocarbamol, Robaxacet 8
How Acetaminophen, Codeine, Methocarbamol interacts with Night Time Superfoods Hot Cocoa — through 7 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Codeine, Methocarbamol interactionJujube Seed ExtractCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, zizyphus might cause additive sedative effects when taken with CNS depressants.
Read the full Jujube Seed Extract + Acetaminophen, Codeine, Methocarbamol interactionChamomile Flower ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants +1 Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP1A2 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Codeine, Methocarbamol interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Codeine, Methocarbamol interactionMagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Acetaminophen, Codeine, Methocarbamol interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Codeine, Methocarbamol interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Codeine, Methocarbamol interactionAcetaminophen, Dichloralantipyrine, IsomethepteneAmidrine, Midchlor, Migquin, Migratine
How Acetaminophen, Dichloralantipyrine, Isometheptene interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Dichloralantipyrine, Isometheptene interactionChamomile Flower ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP1A2 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Dichloralantipyrine, Isometheptene interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Dichloralantipyrine, Isometheptene interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Dichloralantipyrine, Isometheptene interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Dichloralantipyrine, Isometheptene interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Dichloralantipyrine, Isometheptene interactionAcetaminophen, Dichloralphenazone, IsomethepteneMidrin
How Acetaminophen, Dichloralphenazone, Isometheptene interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Dichloralphenazone, Isometheptene interactionJujube Seed ExtractCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, zizyphus might cause additive sedative effects when taken with CNS depressants.
Read the full Jujube Seed Extract + Acetaminophen, Dichloralphenazone, Isometheptene interactionChamomile Flower ExtractCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, German chamomile might have additive effects when used with CNS depressants.
Read the full Chamomile Flower Extract + Acetaminophen, Dichloralphenazone, Isometheptene interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Dichloralphenazone, Isometheptene interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Dichloralphenazone, Isometheptene interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Dichloralphenazone, Isometheptene interactionAcetaminophen, Dichlorophenazone, IsometheptaneIsocom
How Acetaminophen, Dichlorophenazone, Isometheptane interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Dichlorophenazone, Isometheptane interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Dichlorophenazone, Isometheptane interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Dichlorophenazone, Isometheptane interactionChamomile Flower ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP1A2 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Dichlorophenazone, Isometheptane interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Dichlorophenazone, Isometheptane interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Dichlorophenazone, Isometheptane interactionAcetaminophen, DiphenhydramineTylenol PM, Tylenol PM Ex Strength
How Acetaminophen, Diphenhydramine interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Diphenhydramine interactionChamomile Flower ExtractCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, German chamomile might have additive effects when used with CNS depressants.
Read the full Chamomile Flower Extract + Acetaminophen, Diphenhydramine interactionJujube Seed ExtractCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, zizyphus might cause additive sedative effects when taken with CNS depressants.
Read the full Jujube Seed Extract + Acetaminophen, Diphenhydramine interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Diphenhydramine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Diphenhydramine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Diphenhydramine interactionAcetaminophen, Diphenhydramine, PseudoephedrineChildren's Tylenol Allergy, Cold Control, Contac Night Allergy Relief
How Acetaminophen, Diphenhydramine, Pseudoephedrine interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionJujube Seed ExtractCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, zizyphus might cause additive sedative effects when taken with CNS depressants.
Read the full Jujube Seed Extract + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionChamomile Flower ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP1A2 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionAcetaminophen, HydrocodoneAnexsia, Anodynos DHC, Azdone, Co-Gesic, Doucet, Lorcet +9 more
How Acetaminophen, Hydrocodone interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Hydrocodone interactionChamomile Flower ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +2 Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP1A2 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Hydrocodone interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Hydrocodone interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Hydrocodone interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Hydrocodone interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Hydrocodone interactionAcetaminophen, MeperidineDemerol APAP
How Acetaminophen, Meperidine interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants, Serotonergic Drugs Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Meperidine interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Meperidine interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Meperidine interactionChamomile Flower ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants +1 Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP1A2 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Meperidine interactionL-theanineCns Depressants, Serotonergic Drugs Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Meperidine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Meperidine interactionAcetaminophen, OxycodonePercocet, Roxicet, Tylox, Xartemis XR
How Acetaminophen, Oxycodone interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Oxycodone interactionChamomile Flower ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +1 Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP1A2 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Oxycodone interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Oxycodone interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Oxycodone interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Oxycodone interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Oxycodone interactionAcetaminophen, PentazocineTalacen
How Acetaminophen, Pentazocine interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Pentazocine interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Pentazocine interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Pentazocine interactionChamomile Flower ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP1A2 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Pentazocine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Pentazocine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Pentazocine interactionAcetaminophen, PropoxypheneDarvocet-N 100, Darvocet-N 50, E-Lor, Wygesic
How Acetaminophen, Propoxyphene interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Propoxyphene interactionChamomile Flower ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants +1 Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP1A2 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Acetaminophen, Propoxyphene interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetaminophen, Propoxyphene interactionJujube Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might decrease the levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Jujube Seed Extract + Acetaminophen, Propoxyphene interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acetaminophen, Propoxyphene interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Propoxyphene interactionAcetazolamideAk-Zol, Diamox
How Acetazolamide interacts with Night Time Superfoods Hot Cocoa — through 8 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetazolamide interactionJujube Seed ExtractCns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might cause additive sedative effects when taken with CNS depressants.
Read the full Jujube Seed Extract + Acetazolamide interactionChamomile Flower ExtractCns Depressants Moderate
Interaction Summary
Theoretically, German chamomile might have additive effects when used with CNS depressants.
Read the full Chamomile Flower Extract + Acetazolamide interactionReishi Fruiting Body ExtractAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, concurrent use of reishi mushroom with antihypertensive drugs might increase the risk of hypotension.
Read the full Reishi Fruiting Body Extract + Acetazolamide interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Acetazolamide interactionL-theanineAntihypertensive Drugs, Cns Depressants Moderate
Interaction Summary
Theanine might lower blood pressure, potentiating the effects of antihypertensive drugs.
Read the full L-theanine + Acetazolamide interactionSodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Acetazolamide interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetazolamide interactionAlfentanilAlfenta
How Alfentanil interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Alfentanil interactionChamomile Flower ExtractCns Depressants, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, German chamomile might have additive effects when used with CNS depressants.
Read the full Chamomile Flower Extract + Alfentanil interactionJujube Seed ExtractCns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might cause additive sedative effects when taken with CNS depressants.
Read the full Jujube Seed Extract + Alfentanil interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Alfentanil interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Alfentanil interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Alfentanil interactionAlprazolamNiravam, Xanax
How Alprazolam interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Alprazolam interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Alprazolam interactionChamomile Flower ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP3A4 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Alprazolam interactionJujube Seed ExtractCns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might cause additive sedative effects when taken with CNS depressants.
Read the full Jujube Seed Extract + Alprazolam interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Alprazolam interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Alprazolam interactionAluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium HydroxideAscriptin Codeine #2
How Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interacts with Night Time Superfoods Hot Cocoa — through 9 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionJujube Seed ExtractCns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might cause additive sedative effects when taken with CNS depressants.
Read the full Jujube Seed Extract + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionAdaptogen BlendAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, jiaogulan might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full Adaptogen Blend + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionChamomile Flower ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, German chamomile might inhibit CYP2D6 and increase levels of drugs metabolized by these enzymes.
Read the full Chamomile Flower Extract + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionReishi Fruiting Body ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, high doses of reishi mushroom might increase the risk of bleeding.
Read the full Reishi Fruiting Body Extract + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionMagnesiumAnticoagulant/antiplatelet Drugs, Antacids Moderate
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionAminoglutethimideCytadren
How Aminoglutethimide interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Aminoglutethimide interactionJujube Seed ExtractCns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might cause additive sedative effects when taken with CNS depressants.
Read the full Jujube Seed Extract + Aminoglutethimide interactionChamomile Flower ExtractCns Depressants Moderate
Interaction Summary
Theoretically, German chamomile might have additive effects when used with CNS depressants.
Read the full Chamomile Flower Extract + Aminoglutethimide interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Aminoglutethimide interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Aminoglutethimide interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Aminoglutethimide interactionAminophylline, Amobarbital, EphedrineAmesec
How Aminophylline, Amobarbital, Ephedrine interacts with Night Time Superfoods Hot Cocoa — through 6 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Aminophylline, Amobarbital, Ephedrine interactionJujube Seed ExtractCns Depressants Moderate
Interaction Summary
Theoretically, zizyphus might cause additive sedative effects when taken with CNS depressants.
Read the full Jujube Seed Extract + Aminophylline, Amobarbital, Ephedrine interactionSilk Tree Bark ExtractCns Depressants Moderate
Interaction Summary
Animal research suggests that certain constituents from Albizia julibrissin flowers can potentiate pentobarbital-induced sleeping time in mice.
Read the full Silk Tree Bark Extract + Aminophylline, Amobarbital, Ephedrine interactionChamomile Flower ExtractCns Depressants Moderate
Interaction Summary
Theoretically, German chamomile might have additive effects when used with CNS depressants.
Read the full Chamomile Flower Extract + Aminophylline, Amobarbital, Ephedrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Aminophylline, Amobarbital, Ephedrine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Aminophylline, Amobarbital, Ephedrine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Night Time Superfoods Hot Cocoa with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Dietary Fiber
Carbamazepine (Tegretol)
Theoretically, black psyllium might reduce the effects of carbamazepine and increase the risk for convulsions.
Theoretically, black psyllium might reduce carbamazepine absorption. A preliminary study using blond psyllium reported decreased carbamazepine bioavailability due to binding of the drug to psyllium, as well as reduction of available fluid in the gut for dissolution of the drug. This interaction may also occur with black psyllium.
Lithium
Theoretically, taking black psyllium at the same time as lithium might reduce lithium absorption.
The fiber in black psyllium might reduce lithium absorption and plasma levels. Some case reports describe a reduction in plasma lithium levels with concomitant administration of blond psyllium. This was reversed when psyllium was stopped. This interaction may also occur with black psyllium.
Metformin (Glucophage)
Theoretically, black psyllium might increase the therapeutic and adverse effects of metformin.
Animal research shows that concurrent consumption of blond psyllium with metformin slows and increases the absorption of metformin. This interaction may also occur with black psyllium. To avoid changes in absorption, take psyllium 30-60 minutes after metformin.
Olanzapine (Zyprexa)
Theoretically, taking black psyllium at the same time as olanzapine might reduce olanzapine absorption.
The fiber in black psyllium might decrease the absorption of olanzapine. A single case report describes a reduction in the effectiveness of olanzapine when it was concomitantly administered with an unspecified type of psyllium 3 grams orally twice daily. This effect was reversed when psyllium was stopped.
Digoxin (Lanoxin)
Theoretically, taking black psyllium at the same time as digoxin might reduce digoxin absorption and decrease digoxin levels.
Psyllium might bind digoxin in the gut. However, some clinical evidence suggests that psyllium does not impact digoxin absorption.
Ethinyl Estradiol
Theoretically, taking black psyllium at the same time as ethinyl estradiol might alter levels of estradiol.
Concurrent use of blond psyllium with ethinyl estradiol results in a slight increase in the extent of ethinyl estradiol absorption and a slower rate of absorption. This is unlikely to be clinically significant.
Oral Drugs
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Psyllium seems to have variable effects on drug absorption. To avoid changes in absorption, take psyllium 30-60 minutes after oral medications. Animal research shows that blond psyllium delays and increases the absorption of metformin and ethinyl estradiol. Case reports and animal research suggest that blond psyllium might reduce absorption of lithium, digoxin, olanzapine, and carbamazepine. Finally, some pharmacokinetic studies show that psyllium does not affect the absorption of levothyroxine or warfarin. Although many of these studies evaluated blond psyllium, the fiber content in black psyllium may have similar effects.
L-Theanine
Antihypertensive Drugs
Theanine might lower blood pressure, potentiating the effects of antihypertensive drugs.
Animal research shows that theanine can lower blood pressure in spontaneously hypertensive animals. Theoretically, concomitant use of theanine and antihypertensive drugs might potentiate the antihypertensive activity.
Cns Depressants
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants. However, it is unclear if this concern is clinically relevant.
Theoretically, theanine may compete with glutamate and/or increase plasma gamma-aminobutyric acid (GABA) levels, which could cause CNS depression. In one clinical study, some subjects taking oral theanine reported drowsiness.
Serotonergic Drugs
Clinical studies regarding the effects of L-theanine on serotonin levels are conflicting. Some studies suggest it can increase serotonin levels in the brain while others report that it may decrease them. Nevertheless, there have been no reports of l-theanine being a causative agent in serotonergic-related side effects or serotonin syndrome.
L-Tryptophan
Cns Depressants
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Clinical research shows that L-tryptophan can cause fatigue and drowsiness.
Serotonergic Drugs
Theoretically, combining L-tryptophan with serotonergic drugs might cause additive serotonergic effects.
L-tryptophan is a precursor to serotonin. Theoretically, combining serotonergic drugs with L-tryptophan might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders.
Adaptogen Blend
Anticoagulant/Antiplatelet Drugs
Theoretically, jiaogulan might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
In vitro research suggests that jiaogulan has antiplatelet effects.
Antidiabetes Drugs
Theoretically, jiaogulan might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Clinical research shows that jiaogulan can lower blood glucose levels.
Immunosuppressants
Theoretically, jiaogulan might decrease the effectiveness of immunosuppressive therapy.
Clinical and animal studies suggest that jiaogulan can stimulate the immune system.
Magnesium
Levodopa/Carbidopa (Sinemet)
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Clinical research in healthy volunteers shows that taking magnesium oxide 1000 mg with levodopa 100 mg/carbidopa 10 mg reduces the area under the curve (AUC) of levodopa by 35% and of carbidopa by 81%. In vitro and animal research shows that magnesium produces an alkaline environment in the digestive tract, which might lead to degradation and reduced bioavailability of levodopa/carbidopa.
Aminoglycoside Antibiotics
Concomitant use of aminoglycoside antibiotics and magnesium can increase the risk for neuromuscular weakness.
Both aminoglycosides and magnesium reduce presynaptic acetylcholine release, which can lead to neuromuscular blockade and possible paralysis. This is most likely to occur with high doses of magnesium given intravenously.
Antacids
Use of acid reducers may reduce the laxative effect of magnesium oxide.
A retrospective analysis shows that, in the presence of H2 receptor antagonists (H2RAs) or proton pump inhibitors (PPIs), a higher dose of magnesium oxide is needed for a laxative effect. This may also occur with antacids. Under acidic conditions, magnesium oxide is converted to magnesium chloride and then to magnesium bicarbonate, which has an osmotic laxative effect. By reducing acidity, antacids may reduce the conversion of magnesium oxide to the active bicarbonate salt.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after magnesium containing products.
Bisphosphonates
Magnesium can decrease absorption of bisphosphonates.
Cations, including magnesium, can decrease bisphosphonate absorption. Advise patients to separate doses of magnesium and these drugs by at least 2 hours.
Calcium Channel Blockers
Magnesium can have additive effects with calcium channel blockers, although evidence is conflicting.
Magnesium inhibits calcium entry into smooth muscle cells and may therefore have additive effects with calcium channel blockers. Severe hypotension and neuromuscular blockades may occur when nifedipine is used with intravenous magnesium, although some contradictory evidence suggests that concurrent use of magnesium with nifedipine does not increase the risk of neuromuscular weakness. High doses of magnesium could theoretically have additive effects with other calcium channel blockers.
Digoxin
Magnesium salts may reduce absorption of digoxin.
Clinical evidence suggests that treatment with oral magnesium hydroxide or magnesium trisilicate reduces absorption of digoxin from the intestines. This may reduce the blood levels of digoxin and decrease its therapeutic effects.
Potassium-Sparing Diuretics
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Potassium-sparing diuretics also have magnesium-sparing properties, which can counteract the magnesium losses associated with loop and thiazide diuretics. Theoretically, increased magnesium levels could result from concomitant use of potassium-sparing diuretics and magnesium supplements.
Quinolone Antibiotics
Magnesium decreases absorption of quinolones.
Magnesium can form insoluble complexes with quinolones and decrease their absorption. Advise patients to take these drugs at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Skeletal Muscle Relaxants
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Parenteral magnesium shortens the time to onset of skeletal muscle relaxants by about 1 minute and prolongs the duration of action by about 2 minutes. Magnesium potentiates the effects of skeletal muscle relaxants by decreasing calcium-mediated release of acetylcholine from presynaptic nerve terminals, reducing postsynaptic sensitivity to acetylcholine, and having a direct effect on the membrane potential of myocytes. Magnesium also has vasodilatory actions and increases cardiac output, allowing a greater amount of muscle relaxant to reach the motor end plate. A clinical study found that low-dose rocuronium (0.45 mg/kg), when given after administration of magnesium 30 mg/kg over 10 minutes, has an accelerated onset of effect, which matches the onset of effect seen with a full-dose rocuronium regimen (0.6 mg/kg). In another clinical study, onset times for rocuronium doses of 0.3, 0.6, and 1.2 mg/kg were 86, 76, and 50 seconds, respectively, when given alone, but were reduced to 66, 44, and 38 seconds, respectively, when the doses were given after a 15-minute infusion of magnesium sulfate 60 mg/kg. Giving intraoperative intravenous magnesium sulfate, 50 mg/kg loading dose followed by 15 mg/kg/hour, reduces the onset time of rocuronium, enhances its clinical effects, reduces the dose of intraoperative opiates, and prolongs the spontaneous recovery time. It does not affect the activity of subsequently administered neostigmine.
Sulfonylureas
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Clinical research shows that administration of magnesium hydroxide with glyburide increases glyburide absorption, increases maximal insulin response by 35-fold, and increases the risk of hypoglycemia, when compared with glyburide alone. A similar interaction occurs between magnesium hydroxide and glipizide. The mechanism of this effect appears to be related to the elevation of gastrointestinal pH by magnesium-based antacids, increasing solubility and enhancing absorption of sulfonylureas.
Tetracycline Antibiotics
Magnesium decreases absorption of tetracyclines.
Magnesium can form insoluble complexes with tetracyclines in the gut and decrease their absorption and antibacterial activity. Advise patients to take these drugs 1 hour before or 2 hours after magnesium supplements.
Anticoagulant/Antiplatelet Drugs
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
In vitro evidence shows that magnesium sulfate inhibits platelet aggregation, even at low concentrations. Some preliminary clinical evidence shows that infusion of magnesium sulfate increases bleeding time by 48% and reduces platelet activity. However, other clinical research shows that magnesium does not affect platelet aggregation, although inhibition of platelet-dependent thrombosis can occur.
Gabapentin (Neurontin)
Gabapentin absorption can be decreased by magnesium.
Clinical research shows that giving magnesium oxide orally along with gabapentin decreases the maximum plasma concentration of gabapentin by 33%, time to maximum concentration by 36%, and area under the curve by 43%. Advise patients to take gabapentin at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Sevelamer (Renagel, Renvela)
Sevelamer may increase serum magnesium levels.
In patients on hemodialysis, sevelamer use was associated with a 0.28 mg/dL increase in serum magnesium. The mechanism of this interaction remains unclear.
Sodium
Antihypertensive Drugs
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
High intake of dietary sodium can increase systolic and diastolic blood pressure. Also, high intake of sodium may necessitate increased use of antihypertensive medications to achieve blood pressure control in some patients, such as those with chronic kidney disease.
Corticosteroids
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Mineralocorticoids and some glucocorticoids (corticosteroids) cause sodium retention. This effect is dose-related and depends on mineralocorticoid potency. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Didanosine (Videx)
Concomitant use of didanosine with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia.
Didanosine formulations contain a significant amount of sodium.
Lithium
Altering dietary intake of sodium might alter the levels and clinical effects of lithium.
High sodium intake can reduce plasma concentrations of lithium by increasing lithium excretion. Reducing sodium intake can significantly increase plasma concentrations of lithium and cause lithium toxicity in patients being treated with lithium carbonate. Stabilizing sodium intake is shown to reduce the percentage of patients with lithium level fluctuations above 0.8 mEq/L. Patients taking lithium should avoid significant alterations in their dietary intake of sodium.
Sodium Phosphates
Theoretically, concomitant use of sodium phosphate with sodium supplements might increase the risk of hypernatremia.
Use of high doses (> 45 mL in 24 hours) of sodium phosphate, such as those used for bowel cleansing before surgery, can lead to serious electrolyte disturbances, including hypernatremia. The risk of hypernatremia is highest in the elderly and people with other risk factors for electrolyte disturbances.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related complications.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium supplements or high-sodium diets, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Tolvaptan (Samsca)
Theoretically, concomitant use of tolvaptan with sodium might increase the risk of hypernatremia.
Tolvaptan is a vasopressin receptor 2 antagonist that is used to increase sodium levels in patients with hyponatremia. Patients taking tolvaptan should use caution with the use of sodium salts such as sodium chloride.
Iron
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Iron might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide and iron can be taken together if taken with food. However, if taken on an empty stomach, bictegravir/emtricitabine/tenofovir alafenamide should not be taken with, or 2 hours after, iron containing products.
Bisphosphonates
Iron reduces the absorption of bisphosphonates.
Advise patients that doses of bisphosphonates should be separated by at least two hours from doses of all other medications, including supplements such as iron. Divalent cations, including iron, can decrease absorption of bisphosphonates by forming insoluble complexes in the gastrointestinal tract.
Denosumab (Prolia, Others)
Administration of intravenous iron within one month of denosumab administration might increase the risk of severe hypophosphatemia and hypocalcemia.
A case of severe hypocalcemia (albumin corrected calcium 6.88 mg/dL, ionized calcium 3.68 mg/dL) and hypophosphatemia (<0.5 mg/dL) with respiratory acidosis, QT interval prolongation, and nonsustained ventricular tachycardia was reported in a 76-year-old male who had received an iron polymaltose infusion within 2 weeks of a subcutaneous injection of denosumab. Serum parathyroid hormone was also elevated (348 pg/mL). Subsequent iron infusions with iron polymaltose and ferric carboxymaltose were followed by transient hypophosphatemia, but without hypocalcemia. Additionally, a literature review describes 6 additional cases of hypophosphatemia and hypocalcemia in patients 52-92 years of age who had been administered intravenous iron as either ferric carboxymaltose or iron polymaltose and subcutaneous denosumab within 1-4 weeks of each other.
Dolutegravir (Tivicay)
Iron might decrease dolutegravir levels by reducing its absorption.
Advise patients to take dolutegravir at least 2 hours before or 6 hours after taking iron. Pharmacokinetic research shows that iron can decrease the absorption of dolutegravir from the gastrointestinal tract through chelation. When taken under fasting conditions, a single dose of ferrous fumarate 324 mg orally along with dolutegravir 50 mg reduces overall exposure to dolutegravir by 54%.
Integrase Inhibitors
Theoretically, taking iron along with integrase inhibitors might decrease the levels and clinical effects of these drugs.
Iron is a divalent cation. There is concern that iron may decrease the absorption of integrase inhibitors from the gastrointestinal tract through chelation. One pharmacokinetic study shows that iron can decrease blood levels of the specific integrase inhibitor dolutegravir through chelation. Also, other pharmacokinetic research shows that other divalent cations such as calcium can decrease the absorption and levels of some integrase inhibitors through chelation.
Levodopa
Iron might decrease levodopa levels by reducing its absorption.
Advise patients to separate doses of levodopa and iron as much as possible. There is some evidence in healthy people that iron forms chelates with levodopa, reducing the amount of levodopa absorbed by around 50%. The clinical significance of this hasn't been determined.
Levothyroxine (Synthroid, Others)
Iron might decrease levothyroxine levels by reducing its absorption.
Advise patients to separate levothyroxine and iron doses by at least 2 hours. Iron can decrease the absorption and efficacy of levothyroxine by forming insoluble complexes in the gastrointestinal tract.
Methyldopa (Aldomet)
Iron might decrease methyldopa levels by reducing its absorption.
Advise patients to separate methyldopa and iron doses by at least 2 hours. Iron can decrease the absorption of methyldopa from the gastrointestinal tract through chelation, resulting in increases in blood pressure.
Mycophenolate Mofetil (Cellcept)
Theoretically, iron might decrease mycophenolate mofetil levels by reducing its absorption.
Advise patients to take iron 4-6 hours before, or 2 hours after, mycophenolate mofetil. It has been suggested that a decrease of absorption is possible, probably by forming nonabsorbable chelates. However, mycophenolate pharmacokinetics are not affected by iron supplementation in available clinical research.
Penicillamine (Cuprimine, Depen)
Iron might decrease penicillamine levels by reducing its absorption.
Advise patients to separate penicillamine and iron doses by at least 2 hours. Oral iron supplements can reduce absorption of penicillamine by 30% to 70%, probably due to chelate formation. In people with Wilson's disease, this interaction has led to reduced efficacy of penicillamine.
Quinolone Antibiotics
Iron might decrease levels of quinolone antibiotics by reducing their absorption.
Advise patients to separate quinolone antibiotics and iron doses by at least 2 hours. Iron decreases the absorption of quinolones due to formation of insoluble complexes in the gastrointestinal tract.
Tetracycline Antibiotics
Iron might decrease levels of tetracycline antibiotics by reducing their absorption.
Advise patients to take iron at least 2 hours before or 4 hours after tetracycline antibiotics. Concomitant use can decrease absorption of tetracycline antibiotics from the gastrointestinal tract by 50% to 90%.
Chloramphenicol
Theoretically, taking chloramphenicol with iron might reduce the response to iron therapy in iron deficiency anemia.
Chloramphenicol interferes with erythrocyte maturation. However, since chloramphenicol isn't usually taken for prolonged periods, this isn't likely to be clinically significant.
Zinc
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Theoretically, zinc might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after zinc containing products.
Cephalexin (Keflex)
Zinc might decrease cephalexin levels by chelating with cephalexin in the gut and preventing its absorption.
A pharmacokinetic study shows that zinc sulfate 250 mg taken concomitantly with cephalexin 500 mg decreases peak levels of cephalexin by 31% and reduces the exposure to cephalexin by 27%. Also, taking zinc sulfate 3 hours before cephalexin decreases peak levels of cephalexin by 11% and reduces the exposure to cephalexin by 18%. By decreasing cephalexin levels, zinc might increase the risk of treatment failure. This effect does not occur when zinc is taken 3 hours after the cephalexin dose. To avoid an interaction, advise patients take zinc sulfate 3 hours after taking cephalexin.
Cisplatin (Platinol-Aq)
Theoretically, zinc might interfere with the therapeutic effects of cisplatin.
Animal research suggests that zinc stimulates tumor cell production of the protein metallothionein, which binds and inactivates cisplatin. It is not known whether zinc supplements or high dietary zinc intake can cause clinically significant interference with cisplatin therapy. Cisplatin might also increase zinc excretion.
Integrase Inhibitors
Theoretically, taking zinc along with integrase inhibitors might decrease the levels and clinical effects of these drugs.
Zinc is a divalent cation. Pharmacokinetic studies have shown that other divalent cations such as calcium and iron can decrease blood levels of the integrase inhibitor dolutegravir through chelation.
Penicillamine (Cuprimine, Depen)
Zinc might reduce the levels and clinical effects of penicillamine.
By forming an insoluble complex with penicillamine, zinc interferes with penicillamine absorption and activity. Zinc supplements reduce the efficacy of low-dose penicillamine (0.5-1 gram/day), but do not seem to affect higher doses (1-2.75 gram/day), provided dosing times are separated. Advise patients to take zinc and penicillamine at least 2 hours apart.
Quinolone Antibiotics
Zinc can decrease the levels and clinical effects of quinolones antibiotics.
Quinolones form complexes with zinc in the gastrointestinal tract, reducing absorption of both the quinolone and zinc if taken at the same time. Advise patients to take these drugs at least 2 hours before, or 4-6 hours after, zinc supplements.
Ritonavir (Norvir)
Zinc modestly reduces levels of ritonavir.
Clinical research shows that zinc might reduce serum ritonavir levels by chelating with ritonavir in the gut and preventing its absorption. In patients with HIV, ritonavir is taken with atazanavir to prevent the metabolism and increase the effects of atazanavir. A pharmacokinetic study shows that, in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate (Solvazinc tablets) 125 mg as a single dose or as multiple daily doses for 2 weeks reduces plasma levels of ritonavir by about 16%. However, atazanavir levels still remains high enough to prevent HIV virus replication. Therefore, the decrease in ritonavir levels is not likely to be clinically significant.
Tetracycline Antibiotics
Zinc might reduce levels of tetracycline antibiotics.
Tetracyclines form complexes with zinc in the gastrointestinal tract, which can reduce absorption of both the tetracycline and zinc when taken at the same time. Taking zinc sulfate 200 mg with tetracycline reduces absorption of the antibiotic by 30% to 40%. Demeclocycline and minocycline cause a similar interaction. However, doxycycline does not seem to interact significantly with zinc. Advise patients to take tetracyclines at least 2 hours before, or 4-6 hours after, zinc supplements to avoid any interactions.
Amiloride (Midamor)
Amiloride can modestly reduce zinc excretion and increase zinc levels.
Clinical research shows that amiloride can reduce urinary zinc excretion, especially at doses of 10 mg per day or more. This zinc-sparing effect can help to counteract zinc losses caused by thiazide diuretics, but it is unlikely to cause zinc toxicity at usual amiloride doses. The other potassium-sparing diuretics, spironolactone (Aldactone) and triamterene (Dyrenium), do not seem to have a zinc-sparing effect.
Atazanavir (Reyataz)
Zinc modestly reduces levels of atazanavir, although this effect does not seem to be clinically significant.
Clinical research shows that zinc might decrease serum atazanavir levels by chelating with atazanavir in the gut and preventing its absorption. Although a single dose of zinc sulfate (Solvazinc tablets) 125 mg orally does not affect atazanavir concentrations in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate 125 mg daily for 2 weeks reduces plasma levels of atazanavir by about 22% in these patients. However, despite this decrease, atazanavir levels still remain at high enough concentrations for the prevention of HIV virus replication.
Potassium
Ace Inhibitors (Aceis)
Using ACEIs with high doses of potassium increases the risk of hyperkalemia.
ACEIs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Angiotensin Receptor Blockers (Arbs)
Using ARBs with high doses of potassium increases the risk of hyperkalemia.
ARBs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Potassium-Sparing Diuretics
Concomitant use increases the risk of hyperkalemia.
Using potassium-sparing diuretics with potassium supplements increases the risk of hyperkalemia.
Brand information
Manufacturer and brand details for Night Time Superfoods Hot Cocoa, from the product label.
Night Time Superfoods Hot Cocoa by moonbrew: Common Questions
Does Night Time Superfoods Hot Cocoa by moonbrew interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Will this help me sleep?
Is it safe if I'm on blood pressure medication?
Can I take this with my antidepressant?
What are the most common side effects?
Is this safe in pregnancy?
Can I take this while breastfeeding?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Night Time Superfoods Hot Cocoa is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Night Time Superfoods Hot Cocoa’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Sodium
Interacts with 205 drugsSodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets get more than enough—often too much—from...
Read the full Sodium monograph → Herb & supplement monographPotassium
Interacts with 62 drugsPotassium is an essential mineral your body needs for nerve signals, muscle function, and a steady heartbeat, and most people get enough from a balanced diet rich in fruits and vegetables. P...
Read the full Potassium monograph → Herb & supplement monographIron
Interacts with 80 drugsIron is an essential mineral your body needs to make hemoglobin and carry oxygen in the blood. Supplements are mainly useful for treating or preventing iron deficiency and iron-deficiency an...
Read the full Iron monograph → Herb & supplement monographBlack Psyllium
Interacts with 2,025 drugsBlack psyllium is a soluble-fiber supplement made from the seeds of a Plantago plant, used mostly to ease constipation and support digestive health. It is best known and most studied for rel...
Read the full Black Psyllium monograph → Herb & supplement monographJiaogulan
Interacts with 327 drugsJiaogulan is a climbing vine used in traditional Chinese medicine as an adaptogen and for heart, blood sugar, and cholesterol support. Early human and animal studies are promising for some u...
Read the full Jiaogulan monograph → Herb & supplement monographGerman Chamomile
Interacts with 960 drugsGerman chamomile is a widely used herbal remedy taken mainly as a tea for calming, sleep, and digestive complaints. Early research suggests possible benefits for mild anxiety and some skin o...
Read the full German Chamomile monograph → Herb & supplement monographReishi Mushroom
Interacts with 375 drugsReishi is a traditional Asian mushroom widely used to support the immune system and overall wellness. Human evidence for most of its claimed benefits is limited or low-quality, so it should...
Read the full Reishi Mushroom monograph → Herb & supplement monographZizyphus
Interacts with 469 drugsZizyphus (jujube) is an edible fruit and traditional remedy used mainly for sleep, anxiety, and digestion. The fruit is a nutritious food, but human evidence for its medicinal benefits is li...
Read the full Zizyphus monograph → Herb & supplement monographAlbizia Julibrissin
Interacts with 248 drugsAlbizia julibrissin (Persian silk tree, He Huan) is a plant used in traditional Chinese medicine, mainly the flower and bark, for calming the mind, lifting mood, and easing sleep problems. H...
Read the full Albizia Julibrissin monograph → Herb & supplement monographOriental Arborvitae
Oriental Arborvitae is an evergreen conifer used in Traditional Chinese Medicine, where the seeds (Bai Zi Ren) are taken to calm the mind and ease constipation, and the leaves (Ce Bai Ye) ar...
Read the full Oriental Arborvitae monograph → Herb & supplement monographZinc
Interacts with 67 drugsZinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but supplements can help correct or prevent a defici...
Read the full Zinc monograph → Herb & supplement monographMagnesium
Interacts with 295 drugsMagnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preventing or correcting deficiency. Some othe...
Read the full Magnesium monograph → Herb & supplement monographL-tryptophan
Interacts with 394 drugsL-tryptophan is an essential amino acid the body uses to make serotonin and melatonin, and people take it to support sleep and mood. The evidence for supplement use is limited and mixed, and...
Read the full L-tryptophan monograph → Herb & supplement monographTheanine
Interacts with 565 drugsTheanine (usually L-theanine) is an amino acid found naturally in tea leaves that many people take to feel calmer and less stressed without strong drowsiness. Early research suggests it may...
Read the full Theanine monograph →Sources & How We Checked
Night Time Superfoods Hot Cocoa's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 392 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Sodium 38 references
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Food and Drug Administration Science Background: Safety of Sodium Phosphates Oral Solution. September 17, 2001. Available at: http://www.fda.gov/cder/drug/safety/sodiumphospate.htm
- Coton T, Mallaret C, Coilliot C, Carre D, Guisset M. Severe acute ulcerated gastritis induced by salt. Presse Med 2009;38(3):499-500. PubMed
- Frings-Meuthen P, Buehlmeier J, Baecker N, et al. High sodium chloride intake exacerbates immobilization-induced bone resorption and protein losses. J Appl Physiol 2011;111(2):537-542. PubMed
- Frings-Meuthen P, Baecker N, Heer M. Low-grade metabolic acidosis may be the cause of sodium chloride-induced exaggerated bone resorption. J Bone Miner Res 2008;23(4):517-524. PubMed
- Alam S, Johnson AG. A meta-analysis of randomised controlled trials (RCT) among healthy normotensive and essential hypertensive elderly patients to determine the effect of high salt (NaCl) diet of blood pressure. J Hum Hypertens 1999;13(6):367-74.
- Boudville N, Ward S, Benaroia M, House AA. Increased sodium intake correlates with greater use of antihypertensive agents by subjects with chronic kidney disease. Am J Hypertens 2005;18(10):1300-5. PubMed
- Bennett WM. Drug interactions and consequences of sodium restriction. Am J Clin Nutr 1997;65(2 Suppl):678S-681S. PubMed
- Okusa MD, Crystal LJ. Clinical manifestations and management of acute lithium intoxication. Am J Med 1994;97(4):383-9. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary reference intakes for water, potassium, sodium, chloride, and sulfate. Washington, DC: National Academy Press, 2005. Available at: http://www.nap.edu/openbook.php?record_id=10925. DOI
- D'Elia L, Rossi G, Ippolito R, Cappuccio FP, Strazzullo P. Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clin Nutr 2012;31(4):489-98. PubMed
- Goldsmith SR. Hyponatremia in heart failure: time for a trial. J Card Fail 2013;19(6):398-400. PubMed
- Willocks L, Brettle R, Keen J, Valentine C, Pinching AJ. Formulations of didanosine (ddI) and salt overload. Lancet 1992;339(8786):190.
- Chen L, Zhang Z, Chen W, Whelton PK, Appel LJ. Lower Sodium Intake and Risk of Headaches: Results From the Trial of Nonpharmacologic Interventions in the Elderly. Am J Public Health. 2016;106(7):1270-5. PubMed
- Cook NR, Appel LJ, Whelton PK. Lower levels of sodium intake and reduced cardiovascular risk. Circulation. 2014;129(9):981-9. PubMed
- Cook NR, Appel LJ, Whelton PK. Sodium Intake and All-Cause Mortality Over 20 Years in the Trials of Hypertension Prevention. J Am Coll Cardiol. 2016;68(15):1609-1617. PubMed
- Mente A, O'Donnell M, Rangarajan S, et al. Associations of urinary sodium excretion with cardiovascular events in individuals with and without hypertension: a pooled analysis of data from four studies. Lancet. 2016;388(10043):465-75. PubMed
- Moosavian SP, Haghighatdoost F, Surkan PJ, Azadbakht L. Salt and obesity: a systematic review and meta-analysis of observational studies. Int J Food Sci Nutr. 2017;68(3):265-277. PubMed
- O'Donnell M, Mente A, Rangarajan S, et al. Urinary sodium and potassium excretion, mortality, and cardiovascular events. N Engl J Med. 2014;371(7):612-23. DOI
- Poggio R, Gutierrez L, Matta MG, Elorriaga N, Irazola V, Rubinstein A. Daily sodium consumption and CVD mortality in the general population: systematic review and meta-analysis of prospective studies. Public Health Nutr. 2015;18(4):695-704. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Mahtani KR, Heneghan C, Onakpoya I, et al. Reduced Salt Intake for Heart Failure: A Systematic Review. JAMA Intern Med. 2018 Dec 1;178(12):1693-1700. PubMed
- Yancy CW. Sodium Restriction in Heart Failure: Too Much Uncertainty-Do the Trials. JAMA Intern Med. 2018 Dec 1;178(12):1700-1701. PubMed
- He FJ, Campbell NRC, Ma Y, MacGregor GA, Cogswell ME, Cook NR. Errors in estimating usual sodium intake by the Kawasaki formula alter its relationship with mortality: implications for public health. Int J Epidemiol. 2018;47(6):1784-1795. PubMed
- Murthy K, Ondrey GJ, Malkani N, et al. THE EFFECTS OF HYPONATREMIA ON BONE DENSITY AND FRACTURES: A SYSTEMATIC REVIEW AND META-ANALYSIS. Endocr Pract. 2019;25(4):366-378. PubMed
- Messerli FH, Hofstetter L, Syrogiannouli L, et al. Sodium intake, life expectancy, and all-cause mortality. Eur Heart J 2021;42(21):2103-2112. PubMed
- Graudal NA, Hubeck-Graudal T, Jurgens G. Effects of low sodium diet versus high sodium diet on blood pressure, renin, aldosterone, catecholamines, cholesterol, and triglyceride. Cochrane Database Syst Rev 2020;12(12):CD004022. PubMed
- Giatti S, Santos RB, Aielo AN, et al. Association of sodium with obstructive sleep apnea. The ELSA-Brasil study. Ann Am Thorac Soc 2021;18(3):502-510. PubMed
- Nan X, Lu H, Wu J, et al. The interactive association between sodium intake, alcohol consumption and hypertension among elderly in northern China: a cross-sectional study. BMC Geriatr 2021;21(1):135. PubMed
- Kyozuka H, Fukusda T, Murata T, et al. Impact of preconception sodium intake on hypertensive disorders of pregnancy: The Japan Environment and Children's study. Pregnancy Hypertens 2021;23:66-72. PubMed
- Zhao L, Ogden CL, Yang Q, et al. Association of usual sodium intake with obesity among US children and adolescents, NHANES 2009-2016. Obesity (Silver Spring) 2021;29(3):587-594. PubMed
- Ma Y, He FJ, Sun Q, et al. 24-Hour urinary sodium and potassium excretion and cardiovascular risk. N Engl J Med 2022;386(3):252-263. PubMed
- Liu J, Yang X, Zhang P, et al. Association of urinary sodium excretion and left ventricular hypertrophy in people with type 2 diabetes mellitus: A cross-sectional study. Front Endocrinol (Lausanne) 2021;12:728493. PubMed
- Filippini T, Malavolti M, Whelton PK, Vinceti M. Sodium intake and risk of hypertension: A systematic review and dose-response meta-analysis of observational cohort studies. Curr Hypertens Rep 2022;24(5):133-144. PubMed
- Wang DD, Li Y, Nguyen XT, et al. Dietary sodium and potassium intake and risk of non-fatal cardiovascular diseases: The million veteran program. Nutrients 2022;14(5):1121. PubMed
- Kwak JH, Park CH, Eun CS, et al. The associations of dietary intake of high sodium and low zinc with gastric cancer mortality: A prospective cohort study in Korea. Nutr Cancer 2022;74(10):3501-3508. PubMed
- George S, Maiti R, Mishra BR, Jena M, Mohapatra D. Effect of regulated add-on sodium chloride intake on stabilization of serum lithium concentration in bipolar disorder: A randomized controlled trial. Bipolar Disord 2023;25(1):66-75. PubMed
- Zhou TL, Schütten MTJ, Kroon AA, et al. Urinary Sodium Excretion and Salt Intake Are Not Associated With Blood Pressure Variability in a White General Population. J Am Heart Assoc 2023;12(1):e026578. PubMed
Potassium 12 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Gennaro A. Remington: The Science and Practice of Pharmacy. 19th ed. Lippincott: Williams & Wilkins, 1996.
- Whelton PK, He J, Cutler JA, et al. Effects of oral potassium on blood pressure. Meta-analysis of randomized controlled clinical trials. JAMA 1997;277:1624-32. PubMed
- Phillips, C. O., Kashani, A., Ko, D. K., Francis, G., and Krumholz, H. M. Adverse effects of combination angiotensin II receptor blockers plus angiotensin-converting enzyme inhibitors for left ventricular dysfunction: a quantitative review of data from ra DOI
- Altieri, P. I., Herrero, C., Suero, R., and Ortiz, A. Bleeding duodenal ulcer in a patient taking slow-releasing potassium tablets. Bol.Asoc.Med P.R. 1977;69(8):276.
- Raf, L. E. Enteric-coated potassium chloride tablets and ulcer of the small intestine. Acta Chir Scand Suppl 1967;(374):1-87.
- Potassium chloride oral solution [package insert]. Allentown, PA: Lehigh Valley Technologies, Inc.; 2014.
- Potassium chloride injection [package insert]. Lake Forest, IL: Hospira Inc.; 2009.
- Patel RB, Tannenbaum S, Viana-Tejedor A, et al. Serum potassium levels, cardiac arrhythmias, and mortality following non-ST-elevation myocardial infarction or unstable angina: insights from MERLIN-TIMI 36. Eur Heart J Acute Cardiovasc Care 2017 Feb;6(1):1 PubMed
- Malta D, Arcand J, Ravindran A, Floras V, Allard JP, Newton GE. Adequate intake of potassium does not cause hyperkalemia in hypertensive individuals taking medications that antagonize the renin angiotensin aldosterone system. Am J Clin Nutr 2016 Oct;104(4 PubMed
- Keskin M, Kaya A, Tatlisu MA, et al. The effect of serum potassium level on in-hospital and long-term mortality in ST elevation myocardial infarction. Int J cardiol. 2016 Oct 15;221:505-10.
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
Iron 72 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Bruner AB, Joffe A, Duggan AK, et al. Randomized study of cognitive effects of iron supplementation in non- anaemic iron-deficient adolescent girls. Lancet 1996;348:992-6.
- Ullen H, Augustsson K, Gustavsson C, Steineck G. Supplementary iron intake and risk of cancer: reversed causality? Cancer Lett 1997;114:215-6.
- Reunanen A, Takkunen H, Knekt P, et al. Body iron stores, dietary iron intake and coronary heart disease mortality. J Intern Med 1995;238:223-30. PubMed
- Lund EK, Wharf SG, Fairweather-Tait SJ, Johnson IT. Oral ferrous sulfate supplements increase the free radical-generating capacity of feces from healthy volunteers. Am J Clin Nutr 1999;69:250-5.
- Rehman A, Collis CS, Yang M, et al. The effects of iron and vitamin C co-supplementation on oxidative damage to DNA in healthy volunteers. Biochem Biophys Res Comm 1998;246:293-8. PubMed
- Klipstein-Grobusch K, Grobbee DE, den Breeijen JH, et al. Dietary iron and risk of myocardial infarction in the Rotterdam Study. Am J Epidemiol 1999;149:421-8. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Tatro DS, ed. Drug Interactions Facts. Facts and Comparisons Inc., St. Louis, MO. 1999.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Campbell N, Paddock V, Sundaram R. Alteration of methyldopa absorption, metabolism, and blood pressure control by ferrous sulfate and ferrous gluconate. Clin Pharmacol Ther 1988;43:381-6..
- Schumann K, Borch-Iohnsen B, Hentze MW, Marx JJ. Tolerable upper intakes for dietary iron set by the US Food and Nutrition Board (commentary). Am J Clin Nutr 2002;76:499-500. PubMed
- Tuomainen TP, Punnonen K, Nyyssonen K, Salonen JT. Association between body iron stores and the risk of acute myocardial infarction in men. Circulation 1998;97:1461-6.. PubMed
- Salonen JT, Nyyssonen K, Korpela H, et al. High stored iron levels are associated with excess risk of myocardial infarction in Eastern Finnish men. Circulation 1992;86:803-11.. PubMed
- Campbell NRC, Hasinoff B. Ferrous sulfate reduces levodopa bioavailability: Chelation as a possible mechanism. Clin Pharmacol Ther 1989;45:220-5.. PubMed
- Campbell NRC, Hasinoff BB, Stalts H, et al. Ferrous sulfate reduces thyroxine efficacy in patients with hypothyroidism. Ann Int Med 1992;117:1010-3.. PubMed
- Kiechl S, Willeit J, Egger G, et al. Body iron stores and the risk of carotid atherosclerosis: prospective results from the Bruneck study. Circulation 1997;96:3300-07. PubMed
- Comparison of oral iron supplements. Pharmacist's Letter / Prescriber's Letter 2008;24(8):240811.
- Tran T., Wax J. R., Philput C., Steinfeld J. D., Ingardia C. J. Intentional iron overdose in pregnancy--management and outcome. J Emerg Med 2000;18(2):225-228. PubMed
- Toblli J. E., Brignoli, R. Iron(III)-hydroxide polymaltose complex in iron deficiency anemia / review and meta-analysis. Arzneimittelforschung 2007;57(6A):431-438. PubMed
- Köpcke W., Sauerland M. C. Meta-analysis of efficacy and tolerability data on iron proteinsuccinylate in patients with iron deficiency anemia of different severity. Arzneimittelforschung 1995;45(11):1211-1216.
- Campbell N. R., Campbell R. R., Hasinoff B. B. Ferrous sulfate reduces methyldopa absorption: methyldopa: iron complex formation as a likely mechanism. Clin Invest Med 1990;13(6):329-332.
- Morii M., Ueno K., Ogawa A., Kato R., Yoshimura H., Wada K., Hashimoto H., Takada M., Tanaka K., Nakatani T., Shibakawa M. Impairment of mycophenolate mofetil absorption by iron ion. Clin Pharmacol Ther 2000;68(6):613-616. PubMed
- Gelone D. K., Park J. M., Lake K. D. Lack of an effect of oral iron administration on mycophenolic acid pharmacokinetics in stable renal transplant recipients. Pharmacotherapy 2007;27(9):1272-1278. PubMed
- Ducray P. S., Banken L., Gerber M., Boutouyrie B., Zandt H. Absence of an interaction between iron and mycophenolate mofetil absorption. Br J Clin Pharmacol 2006;62(4):492-495. PubMed
- Lorenz M., Wolzt M., Weigel G., Puttinger H., Hörl W. H., Födinger M., Speiser W., Sunder-Plassmann G. Ferrous sulfate does not affect mycophenolic acid pharmacokinetics in kidney transplant patients. Am J Kidney Dis 2004;43(6):1098-1103. PubMed
- Osman M. A., Patel R. B., Schuna A., Sundstrom W. R., Welling P. G. Reduction in oral penicillamine absorption by food, antacid, and ferrous sulfate. Clin Pharmacol Ther 1983;33(4):465-470. PubMed
- Michael, B., Coyne, D. W., Fishbane, S., Folkert, V., Lynn, R., Nissenson, A. R., Agarwal, R., Eschbach, J. W., Fadem, S. Z., Trout, J. R., Strobos, J., and Warnock, D. G. Sodium ferric gluconate complex in hemodialysis patients: adverse reactions compar
- Zhang, X., Ouyang, J., Wieczorek, R., and DeSoto, F. Iron medication-induced gastric mucosal injury. Pathol.Res Pract 2009;205(8):579-581. PubMed
- Barbieri, P. G. [To-day exposure to occupational carcinogens and their effects. The experience of the rubber industry, iron metallurgy, asphalt work and aviculture]. Epidemiol.Prev 2009;33(4-5 Suppl 2):94-105.
- Macedo, A. and Cardoso, S. [Routine iron supplementation in pregnancy]. Acta Med Port. 2010;23(5):785-792.
- Bastide, N. M., Pierre, F. H., and Corpet, D. E. Heme iron from meat and risk of colorectal cancer: a meta-analysis and a review of the mechanisms involved. Cancer Prev Res (Phila) 2011;4(2):177-184. PubMed
- Stevens, R. G. Iron and the risk of cancer. Med Oncol Tumor Pharmacother. 1990;7(2-3):177-181. PubMed
- van den, Hombergh J., Dalderop, E., and Smit, Y. Does iron therapy benefit children with severe malaria-associated anaemia? A clinical trial with 12 weeks supplementation of oral iron in young children from the Turiani Division, Tanzania. J.Trop.Pediatr. PubMed
- Liabeuf S, Gras V, Moragny J, et al. Ulceration of the oral mucosa following direct contact with ferrous sulfate in elderly patients: a case report and a review of the French National Pharmacovigilance Database. Clin Interv Aging. 2014 Apr 25;9:737-40. PubMed
- Qiao L, Feng Y. Intakes of heme iron and zinc and colorectal cancer incidence: a meta-analysis of prospective studies. Cancer Causes Control. 2013 Jun;24(6):1175-83. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Guidelines for the Use of Antiretroviral Agents in HIV-1-Infected Adults and Adolescents: Drug Interactions between Integrase Inhibitors and Other Drugs. AIDSinfo. July 14, 2016. Available at: https://aidsinfo.nih.gov/guidelines/html/1/adult-and-adolescen
- Song I, Borland J, Arya N, Wynne B, Piscitelli S. Pharmacokinetics of dolutegravir when administered with mineral supplements in healthy adult subjects. J Clin Pharmacol. 2015;55(5):490-6. PubMed
- Esan MO, Boele van Hensbroek M, Nkhoma E, et al. Iron supplementation in HIV infected Malawian children with anemia: a double-blind, randomized, controlled trial. Clin Inf Dis 2013;57(11):1626-34.doi:10.1093/cid/cit528. PubMed
- Zlotkin S, Newton S, Aimone AM, et al. Effect of iron fortification on malaria incidence in infants and young children in Ghana: a randomized trial. JAMA 2013;310(9):938-47. PubMed
- Khambalia AZ, Aimone A, Nagubandi P, et al. High maternal iron status, dietary iron intake and iron supplement use in pregnancy and risk of gestational diabetes mellitus: a prospective study and systematic review. Diabet Med. 2016;33(9):1211-21. PubMed
- Kinnunen TI, Luoto R, Helin A, Hemminki E. Supplemental iron intake and the risk of glucose intolerance in pregnancy: re-analysis of a randomised controlled trial in Finland. Matern Child Nutr. 2016;12(1):74-84.
- Low MS, Speedy J, Styles CE, De-Regil LM, Pasricha SR. Daily iron supplementation for improving anaemia, iron status and health in menstruating women. Cochrane Database Syst Rev. 2016;4:CD009747. PubMed
- Melit LE, Marginean CO, Mocanu S, Marginean MO. A rare case of iron-pill induced gastritis in a female teenager: A case report and a review of the literature. Medicine (Baltimore). 2017;96(30):e7550. PubMed
- Neuberger A, Okebe J, Yahav D, Paul M. Oral iron supplements for children in malaria-endemic areas. Cochrane Database Syst Rev. 2016;2:CD006589. PubMed
- Peña-Rosas JP, De-Regil LM, Gomez Malave H, Flores-Urrutia MC, Dowswell T. Intermittent oral iron supplementation during pregnancy. Cochrane Database Syst Rev. 2015;(10):CD009997. PubMed
- Brabin B, Gies S, Roberts SA, et al. Excess risk of preterm birth with periconceptional iron supplementation in a malaria endemic area: analysis of secondary data on birth outcomes in a double blind randomized controlled safety trial in Burkina Faso. Mala PubMed
- Kaundal R, Bhatia P, Jain A, et al. Randomized controlled trial of twice-daily versus alternate-day oral iron therapy in the treatment of iron-deficiency anemia. Ann Hematol 2020;99(1):57-63. PubMed
- Li N, Zhao G, Wu W, et al. The efficacy and safety of vitamin C for iron supplementation in adult patients with iron deficiency anemia: A randomized clinical trial. JAMA Netw Open. 2020;3(11):e2023644.<br> PubMed
- Houston BL, Hurrie D, Graham J, et al. Efficacy of iron supplementation on fatigue and physical capacity in non-anaemic iron-deficient adults: a systematic review of randomised controlled trials. BMJ Open. 2018;8(4):e019240. PubMed
- Koch RM, Tchernodrinski S, Principe DR. Case report: Rapid onset, ischemic-type gastritis after initiating oral iron supplementation. Front Med (Lausanne) 2022;9:1010897. PubMed
- Milman NT. Iron supplementation in pregnant Danish women revisited: Effects on prepartum and postpartum iron deficiency, anemia, serum erythropoietin; including iron status, erythropoietin and anthropometrics in newborns. A randomized, placebo-controlled
- Rogozinska E, Daru J, Nicolaides M, et al. Iron preparations for women of reproductive age with iron deficiency anaemia in pregnancy (FRIDA): a systematic review and network meta-analysis. Lancet Haematol 2021;8(7):e503-e512. PubMed
- Shah AA, Donovan K, Seeley C, et al. Risk of infection associated with administration of intravenous iron: A systematic review and meta-analysis. JAMA Netw Open 2021;4(11):e2133935. PubMed
- Gamad N, Saha PK, Sharma P, Suri V, Chakrabarti A, Saha L. A randomized controlled trial comparing the efficacy, tolerability, and cost of oral iron preparations in iron-deficiency anemia in pregnancy. J Obstet Gynaecol Res 2021;47(11):3828-3841. PubMed
- El-Hawy MA, Abd Al-Salam SA, Bahbah WA. Comparing oral iron bisglycinate chelate, lactoferrin, lactoferrin with iron and iron polymaltose complex in the treatment of children with iron deficiency anemia. Clin Nutr ESPEN 2021;46:367-371. PubMed
- Adams A, Scheckel B, Habsaoui A, et al. Intravenous iron versus oral iron versus no iron with or without erythropoiesis- stimulating agents (ESA) for cancer patients with anaemia: a systematic review and network meta-analysis. Cochrane Database Syst Rev 2 PubMed
- Kancherla K, Constantin H, Kanawati A, Graham E. Iron-induced Hypophosphatemic Osteomalacia-An Atypical Case of Bilateral Femoral Stress Fractures. J Am Acad Orthop Surg Glob Res Rev 2023;7(5):e22. PubMed
- Shi R, Marin JG, Beaulieu M. Skin staining following intravenous iron extravasation in a patient with chronic kidney disease: A case report. Can J Kidney Health Dis 2023;10:20543581231165705. PubMed
- Varandas C, Vieira J, Correia CJ, et al. Hypersensitivity reactions to iron products: 10-year experience in a Portuguese tertiary Centre. Eur Ann Allergy Clin Immunol 2023.
- Jara Vidal M, López García MC, Quílez Toboso RP. Kounis syndrome after intravenous iron administration. Med Clin (Barc) 2023. DOI
- Jara Vidal M, Ruiz de Assín Valverde A, Aznar Rodríguez S. Severe hypophospathemia secondary to intravenous iron. Med Clin (Barc) 2023. DOI
- Samões B, Silva B, Martins A, et al. Hypophosphatemic osteomalacia induced by intravenous iron therapy: a case report. Joint Bone Spine 2023;90(5):105586. PubMed
- Seng NW, Barco JB, Wong MH, et al. Hypophosphatemia related to intravenous iron therapy with ferric carboxymaltose: A case series. Transfus Med 2023. PubMed
- Fernandez-Flores A, Fernandez-Parrado M, Alzoghby-Abi Chaker J, Angulo AG. Axillary cutaneous hemosiderosis in a patient with hyperhidrosis, after intravenous iron infusion. Am J Dermatopathol 2023;45(7):463-465. PubMed
- Ye S, Grill V, Luo J, Nguyen HH. Concurrent Denosumab and Parenteral Iron Therapy Precipitating Severe Hypocalcemia and Hypophosphatemia. JCEM Case Rep 2024;2(2):luae005. PubMed
- Yerigeri K. Hemochromatosis in an Adult Female With Previous Iron Deficiency Anemia on Iron Supplementation. Cureus 2023;15(12):e50166. PubMed
- Meyers M, Salmon M, Libert I, Klášterský J. A meta-analysis on the risk of infection associated with intravenous iron therapy in cancer-associated anaemia: a double-edged sword?. Curr Opin Oncol 2024;36(4):223-232. PubMed
- Short V, Allen R, Earley CJ, et al. A randomized double-blind pilot study to evaluate the efficacy, safety, and tolerability of intravenous iron versus oral iron for the treatment of restless legs syndrome in patients with iron deficiency anemia. Am J Hem PubMed
- Bellos I, Frountzas M, Pergialiotis V. Comparative Risk of Hypophosphatemia Following the Administration of Intravenous Iron Formulations: A Network Meta-Analysis. Transfus Med Rev 2020;34(3):188-194. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
L-tryptophan 18 references
- Messiha FS. Fluoxetine: adverse effects and drug-drug interactions. J Toxicol Clin Toxicol 1993;31:603-30. PubMed
- Devoe LD, Castillo RA, Searle NS. Maternal dietary substrates and human fetal biophysical activity. The effects of tryptophan and glucose on fetal breathing movements. Am J Obstet Gynecol 1986;155:135-9. DOI
- Lieberman HR, Corkin S, Spring BJ. The effects of dietary neurotransmitter precursors on human behavior. Am J Clin Nutr 1985;42:366-70. PubMed
- U. S. Food and Drug Administration, Center for Food Safety and Applied Nutrition, Office of Nutritional Products, Labeling, and Dietary Supplements. Information Paper on L-Tryptophan and 5-hydroxy-L-tryptophan, February 2001.
- Sullivan EA, Kamb ML, Jones JL, et al. The natural history of eosinophilia-myalgia syndrome in a tryptophan-exposed cohort in South Carolina. Arch Intern Med 1996;156:973-9. DOI
- Philen RM, Hill RH, Flanders WD, et al. Tryptophan contaminants associated with eosinophilia-myalgia syndrome. Am J Epidemiol 1993;138:154-9. PubMed
- Bohme A, Wolter M, Hoelzer D. L-tryptophan-related eosinophilia-myalgia syndrome possibly associated with a chronic B-lymphocytic leukemia. Ann Hematol 1998;77:235-8. PubMed
- Singhal AB, Caviness VS, Begleiter AF, et al. Cerebral vasoconstriction and stroke after use of serotonergic drugs. Neurology 2002;58:130-3. PubMed
- Priori R, Conti F, Luan FL, et al. Chronic fatigue: a peculiar evolution of eosinophilia myalgia syndrome following treatment with L-tryptophan in four Italian adolescents. Eur J Pediatr 1994;153:344-6..
- Klein R, Berg PA. A comparative study on antibodies to nucleoli and 5-hydroxytryptamine in patients with fibromyalgia syndrome and tryptophan-induced eosinophilia-myalgia syndrome. Clin Investig 1994;72:541-9.. PubMed
- Simat TJ, Kleeberg KK, Muller B, Sierts A. Synthesis, formation, and occurrence of contaminants in biotechnologically manufactured L-tryptophan. Adv Exp Med Biol 1999;467:469-80.. PubMed
- Shaw K, Turner J, Del Mar C. Tryptophan and 5-hydroxytryptophan for depression. Cochrane Database Syst Rev 2002;(1):CD003198. PubMed
- Kilbourne EM, Philen RM, Kamb ML, Falk H. Tryptophan produced by Showa Denko and epidemic eosinophilia-myalgia syndrome. J Rheumatol Suppl 1996;46:81-8.
- Horwitz RI, Daniels SR. Bias or biology: evaluating the epidemiologic studies of L-tryptophan and the eosinophilia-myalgia syndrome. J Rheumatol Suppl 1996;46:60-72.
- Shapiro S. Epidemiologic studies of the association of L-tryptophan with the eosinophilia-myalgia syndrome: a critique. J Rheumatol Suppl 1996;46:44-58.
- Mayeno AN, Gleich GJ. The eosinophilia-myalgia syndrome: lessons from Germany. Mayo Clin Proc 1994;69:702-4. PubMed
- Carr L, Ruther E, Berg PA, Lehnert H. Eosinophilia-myalgia syndrome in Germany: an epidemiologic review. Mayo Clin Proc 1994;69:620-5. PubMed
- Ullrich SS, Fitzgerald PCE, Giesbertz P, Steinert RE, Horowitz M, Feinle-Bisset C. Effects of intragastric administration of tryptophan on the blood glucose response to a nutrient drink and energy intake, in lean and obese men. Nutrients 2018;10(4). pii: PubMed
Black Psyllium 18 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Etman M. Effect of a bulk forming laxative on the bioavailablility of carbamazepine in man. Drug Dev Ind Pharm 1995;21:1901-6.
- Perlman BB. Interaction between lithium salts and ispaghula husk. Lancet 1990;335:416.
- Vaswani SK, Hamilton RG, Valentine MD, Adkinson NF. Psyllium laxative-induced anaphylaxis, asthma, and rhinitis. Allergy 1996;51:266-8. PubMed
- Lantner RR, Espiritu BR, Zumerchik P, Tobin MC. Anaphylaxis following ingestion of a psyllium-containing cereal. JAMA 1990;264:2534-6. DOI
- Kaplan MJ. Anaphylactic reaction to "Heartwise." N Engl J Med 1990;323:1072-3. DOI
- Nordstrom M, Melander A, Robertsson E, Steen B. Influence of wheat bran and of a bulk-forming ispaghula cathartic on the bioavailability of digoxin in geriatric in-patients. Drug Nutr Interact 1987;5:67-9..
- Robinson DS, Benjamin DM, McCormack JJ. Interaction of warfarin and nonsystemic gastrointestinal drugs. Clin Pharmacol Ther 1971;12:491-5. PubMed
- Garcia JJ, Fernandez N, Diez MJ, et al. Influence of two dietary fibers in the oral bioavailability and other pharmacokinetic parameters of ethinyloestradiol. Contraception 2000;62:253-7. PubMed
- Fernandez N, Lopez C, Díez R, et al. Drug interactions with the dietary fiber Plantago ovata husk. Expert Opin Drug Metab Toxicol 2012;8(11):1377-86.
- Semen plantaginis in: WHO Monographs on Selected Medicinal Plants, volume 1. World Health Organization, Geneva, 1999. Available at http://apps.who.int/medicinedocs/en/d/Js2200e/. Accessed November 26, 1026.
- Code of Federal Regulations, Title 21 (21CFR 101.17). Food labeling warning, notice, and safe handling statements. Available at www.ecfr.gov/cgi-bin/text-idx?SID=20f647d3b74161501f46564b915b4048&mc=true&node=se21.2.101_117&rgn=div8. Accessed December 3, 2
- Code of Federal Regulations, Title 21 (21CFR 201.319). Specific labeling requirements - water-soluble gums, hydrophilic gums, and hydrophilic mucilloids. Available at www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfcfr/CFRSearch.cfm?fr=201.319. Accessed Dece
- Diez R, Garcia JJ, Diez MJ, Sierra M, Sahagun AM, Fernandez N. Influence of Plantago ovata husk (dietary fiber) on the bioavailability and other pharmacokinetic parameters of metformin in diabetic rabbits. BMC Complement Altern Med. 2017 Jun 7;17(1):298. PubMed
- Chiu AC, Sherman SI. Effects of pharmacological fiber supplements on levothyroxine absorption. Thyroid. 1998;8(8):667-71. PubMed
- Merrick C, Madden CA, Capurso NA. A Case of Blunted Orally Disintegrating Olanzapine Effect Due to Coadministered Psyllium. J Clin Psychiatry 2021;82(2):20cr13633. PubMed
German Chamomile 15 references
- Subiza J, Subiza JL, Hinojosa M, et al. Anaphylactic reaction after the ingestion of chamomile tea; a study of cross-reactivity with other composite pollens. J Allergy Clin Immunol 1989;84:353-8. PubMed
- Budzinski JW, Foster BC, Vandenhoek S, Arnason JT. An in vitro evaluation of human cytochrome P450 3A4 inhibition by selected commercial herbal extracts and tinctures. Phytomedicine 2000;7:273-82. PubMed
- Viola H, Wasowski C, Levi de Stein M, et al. Apigenin, a component of Matricaria recutita flowers, is a central benzodiazepine receptors-ligand with anxiolytic effects. Planta Med 1995;61:213-6.
- van Ketel WG. Allergy to Matricaria chamomilla. Contact Dermatitis 1982;8:143. PubMed
- van Ketel WG. Allergy to Matricaria chamomilla. Contact Dermatitis 1987;16:50-1. PubMed
- Hormann HP, Korting HC. Evidence for the efficacy and safety of topical herbal drugs in dermatology: part I: anti-inflammatory agents. Phytomedicine 1994;1:161-71. PubMed
- Avallone R, Zanoli P, Puia G, et al. Pharmacological profile of apigenin, a flavonoid isolated from Matricaria chamomilla. Biochem Pharmacol 2000;59:1387-94. PubMed
- Kassi E, Papoutsi Z, Fokialakis N, et al. Greek plant extracts exhibit selective estrogen receptor modulator (SERM)-like properties. J Agric Food Chem 2004;52:6956-61. PubMed
- Maliakal PP, Wanwimolruk S. Effect of herbal teas on hepatic drug metabolizing enzymes in rats. J Pharm Pharmacol 2001;53:1323-9. PubMed
- Segal R, Pilote L. Warfarin interaction with Matricaria chamomilla. CMAJ 2006;174:1281-2. PubMed
- Loggia RD, Traversa U, Scarcia V, et al. Depressive effects of Chamomilla recutita (L.) Rausch, tubular flowers, on central nervous system in mice. Pharmacol Res Commun 1982;14(2):153-162. PubMed
- Ganzera M, Schneider P, Stuppner H. Inhibitory effects of the essential oil of chamomile (Matricaria recutita L.) and its major constituents on human cytochrome P450 enzymes. Life Sci 2006;78(8):856-861. PubMed
- Benito P, Rodríguez-Perez R, García F, Juste S, Moneo I, Caballero ML. Occupational allergic rhinoconjunctivitis induced by Matricaria chamomilla with tolerance of chamomile tea. J Investig Allergol Clin Immunol. 2014;24(5):369-70. No abstract available.
- Braga FT, Santos AC, Bueno PC, et al. Use of Chamomilla recutita in the prevention and treatment of oral mucositis in patients undergoing hematopoietic stem cell transplantation: a randomized, controlled, phase II clinical trial. Cancer Nurs 2015;38(4):32 PubMed
- Sarris J, Ravindran A, Yatham LN, et al. Clinician guidelines for the treatment of psychiatric disorders with nutraceuticals and phytoceuticals: The World Federation of Societies of Biological Psychiatry (WFSBP) and Canadian Network for Mood and Anxiety T
Theanine 6 references
- Yokogoshi H, Kobayashi M. Hypotensive effect of gamma-glutamylethylamide in spontaneously hypertensive rats. Life Sci 1998;62:1065-8.
- Haskell, C. F., Kennedy, D. O., Milne, A. L., Wesnes, K. A., and Scholey, A. B. The effects of L-theanine, caffeine and their combination on cognition and mood. Biol.Psychol. 2008;77(2):113-122. PubMed
- Yokogoshi, H., Kato, Y., Sagesaka, Y. M., Takihara-Matsuura, T., Kakuda, T., and Takeuchi, N. Reduction effect of theanine on blood pressure and brain 5-hydroxyindoles in spontaneously hypertensive rats. Biosci.Biotechnol.Biochem. 1995;59(4):615-618. PubMed
- Lyon MR, Kapoor MP, Juneja LR. The effects of L-theanine (Suntheanine®) on objective sleep quality in boys with attention deficit hyperactivity disorder (ADHD): a randomized, double-blind, placebo-controlled clinical trial. Altern Med Rev. 2011;16(4):348-
- Hidese S, Ota M, Wakabayashi C, et al. Effects of chronic l-theanine administration in patients with major depressive disorder: an open-label study. Acta Neuropsychiatr 2017;29(2):72-9.
- Tsuchiya T, Honda H, Oikawa M, et al. Oral administration of the amino acids cystine and theanine attenuates the adverse events of S-1 adjuvant chemotherapy in gastrointestinal cancer patients. Int J Clin Oncol 2016;21(6):1085-90. PubMed
Zinc 88 references
- Barceloux DG. Zinc. J Toxicol Clin Toxicol 1999;37:279-92.
- Eby GA, Davis DR, Halcomb WW. Reduction in duration of common colds by zinc gluconate lozenges in a double-blind study. Antimicrob Agents Chemother 1984;25:20-4. DOI
- Smith DS, Helzner EC, Nuttall CE Jr, et al. Failure of zinc gluconate in treatment of acute upper respiratory tract infections. Antimicrob Agents Chemother 1989;33:646-8. PubMed
- Blondeau JM. Expanded activity and utility of the new fluoroquinolones: a review. Clin Ther 1999;21:3-40. PubMed
- Reyes AJ, Olhaberry JV, Leary WP, et al. Urinary zinc excretion, diuretics, zinc deficiency and some side-effects of diuretics. S Afr Med J 1983;64:936-41.
- Kugelmas M. Preliminary observation: oral zinc sulfate replacement is effective in treating muscle cramps in cirrhotic patients. J Am Coll Nutr 2000;19:13-5. PubMed
- Hebel SK, ed. Drug Facts and Comparisons. 52nd ed. St. Louis: Facts and Comparisons, 1998.
- Chan S, Gerson B, Subramaniam S. The role of copper, molybdenum, selenium, and zinc in nutrition and health. Clin Lab Med 1998;18:673-85. DOI
- Brewer GJ, Yuzbasiyan-Gurkan V, Johnson V, et al. Treatment of Wilson's disease with zinc: XI. Interaction with other anticopper agents. J Am Coll Nutr 1993;12:26-30. PubMed
- Fosmire GJ. Zinc toxicity. Am J Clin Nutr 1990;51:225-7.
- Lomaestro BM, Bailie GR. Absorption interactions with fluoroquinolones. 1995 update. Drug Saf 1995;12:314-33. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Seelig MS. Auto-immune complications of D-penicillamine - A possible result of zinc and magnesium depletion and of pyridoxine inactivation. J Am Coll Nutr 1982;1:207-14. PubMed
- Neuvonen PJ. Interactions with the absorption of tetracyclines. Drugs 1976;11:45-54.. PubMed
- Hirt M, Nobel S, Barron E. Zinc nasal gel for the treatment of common cold symptoms: A double-blind, placebo-controlled trial. Ear Nose Throat J 2000;79:778-82.. DOI
- Simkin PA. Oral zinc sulphate in rheumatoid arthritis. Lancet 1976;2:539-42. PubMed
- Wray D. A double-blind trial of systemic zinc sulfate in recurrent aphthous stomatitis. Oral Surg Oral Med Oral Pathol 1982;53:469-72. PubMed
- Douglas RM, Miles HB, Moore BW, et al. Failure of effervescent zinc acetate lozenges to alter the course of upper respiratory tract infections in Australian adults. Antimicrob Agents Chemother 1987;31:1263-5. PubMed
- Lagiou P, Wuu J, Trichopoulou A, et al. Diet and benign prostatic hyperplasia: a study in Greece. Urology 1999;54:284-90. PubMed
- Ewing CI, Gibbs AC, Ashcroft C, David TJ. Failure of oral zinc supplementation in atopic eczema. Eur J Clin Nutr 1991;45:507-10.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Age-Related Eye Disease Study Research Group. A randomized, placebo-controlled, clinical trial of high-dose supplementation with vitamins C and E, beta carotene, and zinc for age-related macular degeneration and vision loss. AREDS report no. 8. Arch Oph
- Greenberg JE, Lynn M, Kirsner RS, et al. Mucocutaneous pigmented macule as a result of zinc deposition. J Cutan Pathol 2002;29:613-5. PubMed
- Godfrey HR, Godfrey NJ, Godfrey JC, Riley D. A randomized clinical trial on the treatment of oral herpes with topical zinc oxide/glycine. Altern Ther Health Med 2001;7:49-56.
- Turner RB. Ineffectiveness of intranasal zinc gluconate for prevention of experimental rhinovirus colds. Clin Infect Dis 2001;33:1865-70. PubMed
- Belongia EA, Berg R, Liu K. A randomized trial of zinc nasal spray for the treatment of upper respiratory illness in adults. Am J Med 2001;111:103-8. PubMed
- Mossad SB. Effect of zincum gluconicum nasal gel on the duration and symptom severity of the common cold in otherwise healthy adults. QJM 2003;96:35-43. DOI
- Leitzmann MF, Stampfer MJ, Wu K, et al. Zinc supplement use and risk of prostate cancer. J Natl Cancer Inst 2003;95:1004-7.. PubMed
- Jafek BW, Linschoten M, Murrow BW. Zicam Induced Anosmia. American Rhinologic Society 49th Annual Fall Scientific Meeting abstract. Orlando, Florida. September 20, 2003. http://app.american-rhinologic.org/programs/2003ARSFallProgram071503.pdf (Accessed 24
- Uebayashi H, Hatanaka T, Kanemura F, Tonosaki K. Acute anosmia in the mouse: behavioral discrimination among the four basic taste substances. Physiol Behav 2001;72:291-6.. PubMed
- Barrett S. Zicam Marketers Sued. United States District Court Western District of Michigan Southern Division, Filed October 14, 2003, Case No. 4:03CV0146.
- Bilici M, Yildirim F, Kandil S, et al. Double-blind, placebo-controlled study of zinc sulfate in the treatment of attention deficit hyperactivity disorder. Prog Neuropsychopharmacol Biol Psychiatry 2004;28:181-90.. PubMed
- Polk RE, Healy DP, Sahai J, et al. Effect of ferrous sulfate and multivitamins with zinc on absorption of ciprofloxacin in normal volunteers. Antimicrob Agents Chemother 1989;33:1841-4. PubMed
- Mery C, Delrieu F, Ghozlan R, et al. Controlled trial of D-penicillamine in rheumatoid arthritis. Dose effect and the role of zinc. Scand J Rheumatol 1976;5:241-7. PubMed
- Penttila O, Hurme H, Neuvonen PJ. Effect of zinc sulfate on the absorption of tetracycline and doxycycline in man. Eur J Clin Pharmacol 1975;9:131-4.
- Kondo Y, Yamagata K, Satoh M, et al. Optimal administration schedule of cisplatin for bladder tumor with minimal induction of metallothionein. J Urol 2003;170:2467-70. PubMed
- Doz F, Berens ME, Deschepper CF, et al. Experimental basis for increasing the therapeutic index of cis-diamminedicarboxylatocyclobutaneplatinum(II) in brain tumor therapy by a high-zinc diet. Cancer Chemother Pharmacol 1992;29:219-26.
- Wester PO. Urinary zinc excretion during treatment with different diuretics. Acta Med Scand 1980;208:209-12. PubMed
- Golik A, Modai D, Weissgarten J, et al. Hydrochlorothiazide-amiloride causes excessive urinary zinc excretion. Clin Pharmacol Ther 1987;42:42-4. PubMed
- Leary WP, Reyes AJ, Van der Byl K. Urinary magnesium and zinc excretion after two different single doses of amiloride in healthy adults. Curr Ther Res 1983;34:205-16.
- McBride K, Slotnick B, Margolis FL. Does intranasal application of zinc sulfate produce anosmia in the mouse? An olfactometric and anatomical study. Chem Senses 2003;28:659-70. PubMed
- Burd GD. Morphological study of the effects of intranasal zinc sulfate irrigation on the mouse olfactory epithelium and olfactory bulb. Microsc Res Tech 1993;24:195-213. PubMed
- Ducray A, Bondier JR, Michel G, et al. Recovery following peripheral destruction of olfactory neurons in young and adult mice. Eur J Neurosci 2002;15:1907-17. PubMed
- Mayer AD, Rosenblatt JS. Peripheral olfactory deafferentation of the primary olfactory system in rats using ZnSO4 nasal spray with special reference to maternal behavior. Physiol Behav 1993;53:587-92. PubMed
- DeCook CA, Hirsch AR. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Tisdall FF, Brown A, Defries RD. Persistent anosmia following zinc sulfate nasal spraying. JPed 1938;18:60-2. DOI
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Public Health Advisory. Loss of sense of smell with intranasal cold remedies containing zinc. U.S. Food and Drug Administration, June 16, 2009. Available at: http://www.fda.gov/Drugs/DrugSafety/PublicHealthAdvisories/ucm166059.htm (Accessed 16 June 2009)
- Dooren JC. FDA warns against use of Zicam. The Wall Street Journal, June 16, 2009. Available at: http://online.wsj.com/article/SB124516778692319231.html#mod=djemHL?mg=com-wsj (Accessed 16 June 2009).
- Alexander TH, Davidson TM. Intranasal zinc and anosmia: the zinc-induced anosmia syndrome. Laryngoscope 2006;116:217-20.
- Health Canada / GlaxoSmithKline Consumer Healthcare. Association of long-term, excessive use of zinc-containing Poli-Grip products with myeloneuropathy and blood dyscrasias. February 18, 2010. Available at: http://hc-sc.gc.ca/dhp-mps/alt_formats/pdf/medef
- GlaxoSmithKline Consumer Advisory. GlaxoSmithKline (GSK) warns about a potential health risk associated with long-term, excessive use of GSK's zinc-containing denture adhesives Super Polygrip Original, Ultra Fresh and Extra Care. February 18, 2010. Availa
- Science M, Johnstone J, Roth DE, et al. Zinc for the treatment of the common cold: a systematic review and meta-analysis of randomized controlled trials. CMAJ 2012;184:E551-61. PubMed
- Castilla-Higuero, L., Romero-Gomez, M., Suarez, E., and Castro, M. Acute hepatitis after starting zinc therapy in a patient with presymptomatic Wilson's disease. Hepatology 2000;32(4 Pt 1):877. PubMed
- Sharquie, K. E., Najim, R. A., Farjou, I. B., and Al Timimi, D. J. Oral zinc sulphate in the treatment of acute cutaneous leishmaniasis. Clin.Exp.Dermatol. 2001;26(1):21-26. PubMed
- Dreno, B., Moyse, D., Alirezai, M., Amblard, P., Auffret, N., Beylot, C., Bodokh, I., Chivot, M., Daniel, F., Humbert, P., Meynadier, J., and Poli, F. Multicenter randomized comparative double-blind controlled clinical trial of the safety and efficacy of
- Moore, R. Bleeding gastric erosion after oral zinc sulphate. Br.Med J 3-25-1978;1(6115):754. PubMed
- Jafek, B. W., Linschoten, M. R., and Murrow, B. W. Anosmia after intranasal zinc gluconate use. Am J Rhinol. 2004;18(3):137-141. DOI
- Simonart, T. and de, Maertelaer, V. Systemic treatments for cutaneous warts: a systematic review. J Dermatolog.Treat. 2012;23(1):72-77. PubMed
- Cochran, R. J., Tucker, S. B., and Flannigan, S. A. Topical zinc therapy for acne vulgaris. Int.J Dermatol. 1985;24(3):188-190. DOI
- Morgan, A. A. Bleeding gastric erosion after oral zinc sulphate. Br.Med.J. 5-13-1978;1(6122):1283-1284. PubMed
- Murphy, J. V. Intoxication following ingestion of elemental zinc. JAMA 6-22-1970;212(12):2119-2120.
- Lang, C. J., Rabas-Kolominsky, P., Engelhardt, A., Kobras, G., and Konig, H. J. Fatal deterioration of Wilson's disease after institution of oral zinc therapy. Arch Neurol. 1993;50(10):1007-1008. PubMed
- Fjellner, B. Drug-induced lupus erythematosus aggravated by oral zinc therapy. Acta Derm.Venereol. 1979;59(4):368-370. DOI
- Varas Lorenzo, M. J. Zinc acexamate and ranitidine in the short- and mid-term management of gastroduodenal ulcers. Curr Ther Res 21986;39:19-29.
- Bosch, F. and Jimenez, E. Post-marketing surveillance of zinc acexamate in peptic ulcer treatment. Clin Trials J 1990;27:301-312.
- DeCook, C. A. and Hirsch, A. R. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Crown LA, May JA. Zinc toxicity: denture adhesives, bone marrow failure and polyneuropathy. Tenn Med. 2012 Feb;105(2):39-40, 42.
- Dadamio J, Van Tournout M, Teughels W, Dekeyser C, Coucke W, Quirynen M. Efficacy of different mouthrinse formulations in reducing oral malodour: a randomized clinical trial. J Clin Periodontol. 2013 May;40(5):505-13. PubMed
- Moyle G, Else L, Jackson A, Back D, Yapa MH, Seymour N, Ringner-Nackter L, Karolia Z, Gazzard B, Boffito M. Coadministration of atazanavir-ritonavir and zinc sulfate: impact on hyperbilirubinemia and pharmacokinetics. Antimicrob Agents Chemother. 2013 Aug PubMed
- Zittel S, Ufer F, Gerloff C, Münchau A, Rosenkranz M. Severe myelopathy after denture cream use--is copper deficiency or excess zinc the cause? Clin Neurol Neurosurg. 2014 Jun;121:17-8. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Guidelines for the Use of Antiretroviral Agents in HIV-1-Infected Adults and Adolescents: Drug Interactions between Integrase Inhibitors and Other Drugs. AIDSinfo. July 14, 2016. Available at: https://aidsinfo.nih.gov/guidelines/html/1/adult-and-adolescen
- Ding Y, Jia YY, Li F, et al. The effect of staggered administration of zinc sulfate on the pharmacokinetics of oral cephalexin. Br J Clin Pharmacol. 2012 Mar;73(3):422-7. PubMed
- Fallah R, Sabbaghzadegan S, Karbasi SA, Binesh F. Efficacy of zinc sulfate supplement on febrile seizure recurrence prevention in children with normal serum zinc level: A randomised clinical trial. Nutrition. 2015;31(11-12):1358-61. PubMed
- Lazzerini M, Wanzira H. Oral zinc for treating diarrhoea in children. Cochrane Database Syst Rev. 2016;12:CD005436. PubMed
- Mahmoud AM, Al-Alem U, Dabbous F, et al. Zinc intake and risk of prostate cancer: Case-control study and meta-analysis. PLoS One. 2016;11(11):e0165956. PubMed
- Nagraj SK, George RP, Shetty N, Levenson D, Ferraiolo DM, Shrestha A. Interventions for managing taste disturbances. Cochrane Database Syst Rev. 2017 Dec 20;12(12):CD010470. PubMed
- Yee BE, Richards P, Sui JY, Marsch AF. Serum zinc levels and efficacy of zinc treatment in acne vulgaris: A systematic review and meta-analysis. Dermatol Ther. 2020:e14252. PubMed
- Janyajirawong R, Vilaichone RK, Sethasine S. Efficacy of zinc supplement in minimal hepatic encephalopathy: A prospective, randomized controlled study (Zinc-MHE Trial). Asian Pac J Cancer Prev 2021;22(9):2879-2887. PubMed
- Nakano M, Nakamura Y, Miyazaki A, Takahashi J. Zinc pharmacotherapy for elderly osteoporotic patients with zinc deficiency in a clinical setting. Nutrients 2021;13(6):1814. PubMed
- Tolino E, Skroza N, Mambrin A, et al. An open-label study comparing oral zinc to lymecycline in the treatment of acne vulgaris. J Clin Aesthet Dermatol 2021;14(5):56-58.
- Hunter J, Arentz S, Goldenberg J, et al. Zinc for the prevention or treatment of acute viral respiratory tract infections in adults: a rapid systematic review and meta-analysis of randomised controlled trials. BMJ Open. 2021;11(11):e047474. PubMed
- Yamazaki K, Kageyama H, Fujiyama T, Ito T, Urano S, Honda T. A case of systemic contact dermatitis due to zinc supplements. Int J Dermatol 2022. PubMed
- Magham K, Han J, Eilbert W, Bunney EB. Severe copper deficiency anemia caused by zinc supplement use. Am J Emerg Med 2023;72:222. PubMed
- Sivakumar RR, Chinnaiah Govindareddy D, Sahoo J, Bobby Z, Chinnakali P. Effect of daily zinc supplementation for 12 weeks on serum thyroid auto-antibody levels in children and adolescents with autoimmune thyroiditis - a randomized controlled trial. J Pedi PubMed
- AlDhasee O, AlMalki H, AlKharashi N, AlJeraisy N, Al Deeb M. Acute zinc sulfate overdose: clinical presentation and management. BMJ Case Rep 2025;18(1):e263899. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Reishi Mushroom 17 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Tao J, Feng KY. Experimental and clinical studies on inhibitory effect of ganoderma lucidum on platelet aggregation. J Tongji Med Univ 1990;10:240-3. PubMed
- Singh AB, Gupta SK, Pereira BM, Prakash D. Sensitization to Ganoderma lucidum in patients with respiratory allergy in India. Clin Exp Allergy 1995;25:440-7.
- Lee SY, Rhee HM. Cardiovascular effects of mycelium extract of Ganoderma lucidum: inhibition of sympathetic outflow as a mechanism of its hypotensive action. Chem Pharm Bull (Tokyo) 1990;38:1359-64. PubMed
- Kwok Y, Ng KFJ, Li, CCF, et al. A prospective, randomized, double-blind, placebo-controlled study of the platelet and global hemostatic effects of Ganoderma lucidum (Ling-Zhi) in healthy volunteers. Anesth Analg 2005;101:423-6. PubMed
- Wanmuang, H., Leopairut, J., Kositchaiwat, C., Wananukul, W., and Bunyaratvej, S. Fatal fulminant hepatitis associated with Ganoderma lucidum (Lingzhi) mushroom powder. J Med Assoc Thai. 2007;90(1):179-181.
- Seto, S. W., Lam, T. Y., Tam, H. L., Au, A. L., Chan, S. W., Wu, J. H., Yu, P. H., Leung, G. P., Ngai, S. M., Yeung, J. H., Leung, P. S., Lee, S. M., and Kwan, Y. W. Novel hypoglycemic effects of Ganoderma lucidum water-extract in obese/diabetic (+db/+db
- Chu, T. T., Benzie, I. F., Lam, C. W., Fok, B. S., Lee, K. K., and Tomlinson, B. Study of potential cardioprotective effects of Ganoderma lucidum (Lingzhi): results of a controlled human intervention trial. Br.J.Nutr. 2012;107(7):1017-1027.
- Jin, X., Ruiz, Beguerie J., Sze, D. M., and Chan, G. C. Ganoderma lucidum (Reishi mushroom) for cancer treatment. Cochrane.Database.Syst.Rev. 2012;6:CD007731.
- Kabir, Y., Kimura, S., and Tamura, T. Dietary effect of Ganoderma lucidum mushroom on blood pressure and lipid levels in spontaneously hypertensive rats (SHR). J Nutr Sci Vitaminol.(Tokyo) 1988;34(4):433-438. PubMed
- Kanmatsuse, K., Kajiwara, N., Hayashi, K., Shimogaichi, S., Fukinbara, I., Ishikawa, H., and Tamura, T. [Studies on Ganoderma lucidum. I. Efficacy against hypertension and side effects]. Yakugaku Zasshi 1985;105(10):942-947. PubMed
- Gao, Y., Lan, J., Dai, X., Ye, J., and Zhou, S. A Phase I/II Study of Ling Zhi Mushroom Ganoderma lucidum(W.Curt: Fr.) Lloyd (Aphyllophoromycetideae) Extract in Patients with Type II Diabetes Mellitus. International Journal of Medicinal Mushrooms 2004;6. DOI
- Jin H, Zhang G, Cao X, and et al. Treatment of hypertension by linzhi combined with hypotensor and its effects on arterial, arteriolar and capillary pressure and microcirculation. In: Niimi H, Xiu RJ, Sawada T, and et al. Microcirculatory Approach to Asi
- Klupp NL, Chang D, Hawke F, Kiat H, Cao H, Grant SJ, Bensoussan A. Ganoderma lucidum mushroom for the treatment of cardiovascular risk factors. Cochrane Database Syst Rev. 2015 Feb 17;2:CD007259. PubMed
- Zhao H, Zhang Q, Zhao L, Huang X, Wang J, Kang X. Spore Powder of Ganoderma lucidum Improves Cancer-Related Fatigue in Breast Cancer Patients Undergoing Endocrine Therapy: A Pilot Clinical Trial. Evid Based Complement Alternat Med. 2012;2012:809614.
- Pazzi F, Adsuar JC, Domínguez-Muñoz FJ, García-Gordillo MA, Gusi N, Collado-Mateo D. Ganoderma lucidum effects on mood and health-related quality of life in women with fibromyalgia. Healthcare (Basel) 2020;8(4):520. PubMed
- Kogure T, Koiwai A, Fukushi D, et al. Hypereosinophilia with hepatic nodule formation caused by Ganoderma lucidum. Intern Med 2021;60(24):3897-3903.
Zizyphus 15 references
- Adzu, B., Amos, S., Dzarma, S., Wambebe, C., and Gamaniel, K. Effect of Zizyphus spina-christi Willd aqueous extract on the central nervous system in mice. J Ethnopharmacol. 2002;79(1):13-16.
- Cisse, A., Ndiaye, A., Lopez-Sall, P., Seck, F., Faye, B., and Faye, B. [Antidiabetic activity of Zizyphus mauritiana Lam (Rhamnaceae)]. Dakar Med 2000;45(2):105-107.
- Abdel-Zaher, A. O., Salim, S. Y., Assaf, M. H., and Abdel-Hady, R. H. Antidiabetic activity and toxicity of Zizyphus spina-christi leaves. J Ethnopharmacol. 10-3-2005;101(1-3):129-138. PubMed
- Nesseem, D. I., Michel, C. G., Sleem, A. A., and El-Alfy, T. S. Formulation and evaluation of antihyperglycemic leaf extracts of Zizyphus spina-christi (L.) Willd. Pharmazie 2009;64(2):104-109. DOI
- Anand, K. K., Singh, B., Chand, D., Chandan, B. K., and Gupta, V. N. Effect of Zizyphus sativa leaves on blood glucose levels in normal and alloxan-diabetic rats. J Ethnopharmacol. 1989;27(1-2):121-127. PubMed
- Morishita, S., Mishima, Y., Hirai, Y., Saito, T., and Shoji, M. Pharmacological studies of water extract of the Zizyphus seed and the Zizyphus seed containing drug. Gen Pharmacol 1987;18(6):637-641. PubMed
- Watanabe, I., Saito, H., and Takagi, K. Pharmacological studies of Zizyphus seeds. Jpn J Pharmacol 1973;23(4):563-571. DOI
- Wu, S. X., Zhang, J. X., Xu, T., Li, L. F., Zhao, S. Y., and Lan, M. Y. [Effects of seeds, leaves and fruits of Ziziphus spinosa and jujuboside A on central nervous system function]. Zhongguo Zhong Yao Za Zhi 1993;18(11):685-4.
- Glombitza, K. W., Mahran, G. H., Mirhom, Y. W., Michel, K. G., and Motawi, T. K. Hypoglycemic and antihyperglycemic effects of Zizyphus spina-christi in rats. Planta Med 1994;60(3):244-247.
- Jarald, E. E., Joshi, S. B., and Jain, D. C. Antidiabetic activity of extracts and fraction of <it>Zizyphus mauritiana. Pharmaceutical Biology 2009;47:328-334.
- Ebrahimimd S, Ashkani-Esfahani S, Poormahmudibs A. Investigating the efficacy of zizyphus jujuba on neonatal jaundice. Iran J Pediatr. 2011 Sep;21(3):320-4.
- Hajhashemi V, Safaei A. Hypnotic effect of Coriandrum sativum, Ziziphus jujuba, Lavandula angustifolia and Melissa officinalis extracts in mice. Res Pharm Sci. 2015 Nov-Dec;10(6):477-84.
- Jing XY, Peng YR, Wang XM, Duan JA. Effects of Ziziphus jujuba fruit extracts on cytochrome P450 (CYP1A2) activity in rats. Chin J Nat Med. 2015 Aug;13(8):588-94. PubMed
- Irannejad Niri Z, Shidfar F, Jabbari M, et al. The effect of dried Ziziphus vulgaris on glycemic control, lipid profile, apo-proteins and hs-CRP in patients with type 2 diabetes mellitus: a randomized controlled clinical trial. J Food Biochem 2020; Mar 30
- Shergis JL, Hyde A, Meaklim H, Varma P, Da Costa C, Jackson ML. Medicinal seeds Ziziphus spinosa for insomnia: a randomized, placebo-controlled, cross-over, feasibility clinical trial. Complement Ther Med 2021;57:102657. PubMed
Albizia Julibrissin 1 reference
- Kang, T. H., Jeong, S. J., Kim, N. Y., Higuchi, R., and Kim, Y. C. Sedative activity of two flavonol glycosides isolated from the flowers of Albizzia julibrissin Durazz. J Ethnopharmacol 2000;71(1-2):321-323. PubMed
Jiaogulan 8 references
- The Review of Natural Products by Facts and Comparisons. St. Louis, MO: Wolters Kluwer Co., 1999.
- Tan H, Liu ZL, Liu MJ. [Antithrombotic effect of Gynostemma pentaphyllum]. Zhingguo Zhong Xi Yi Jie He Za Zhi 1993;13:278-80.
- Chan LY, Chiu PY, Lau TK. An in-vitro study of ginsenoside Rb(1)-induced teratogenicity using a whole rat embryo culture model. Hum Reprod 2003;18:2166-8..
- Huyen VT, Phan DV, Thang P, Hoa NK, Ostenson CG. Gynostemma pentaphyllum Tea Improves Insulin Sensitivity in Type 2 Diabetic Patients. J Nutr Metab. 2013;2013:765383. doi: 10.1155/2013/765383.
- Li Y, Lin W, Huang J, Xie Y, Ma W. Anti-cancer effects of Gynostemma pentaphyllum (Thunb.) Makino (Jiaogulan). Chin Med. 2016 Sep 27;11:43. Review. PubMed
- Huyen VT, Phan DV, Thang P, Ky PT, Hoa NK, Ostenson CG. Antidiabetic effect of add-on Gynostemma pentaphyllum extract therapy with sulfonylureas in type 2 diabetic patients. Evid Based Complement Alternat Med 2012; 452313.
- Huyen VT, Phan DV, Thang P, Hoa NK, Ostenson CG. Antidiabetic effect of Gynostemma pentaphyllum tea in randomly assigned type 2 diabetic patients. Horm Metab Res. 2010;42(5):353-7.
- Rao A, Clayton P, Briskey D. The effect of an orally-dosed Gynostemma pentaphyllum extract (ActivAMP®) on body composition in overweight, adult men and women: a double-blind, randomised, placebo-controlled study. J Hum Nutr Diet 2021.
Magnesium 82 references
- Rodin SM, Johnson BF. Pharmacokinetic interactions with digoxin. Clin Pharmacokinet 1988;15:227-44.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Dahle LO, Berg G, Hammar M, et al. The effect of oral magnesium substitution on pregnancy-induced leg cramps. Am J Obstet Gynecol 1995;173:175-80. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Peikert A, Wilimzig C, Kohne-Volland R. Prophylaxis of migraine with oral magnesium: results from a prospective, multi-center, placebo-controlled and double-blind randomized study. Cephalalgia 1996;16:257-63. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Washington, DC: National Academy Press, 1999. Available at: http://books.nap.edu/books/0309063507/html/index.html.
- Birrer RB, Shallash AJ, Totten V. Hypermagnesemia-induced fatality following epsom salt gargles. J Emerg Med 2002;22:185-8. PubMed
- Ryan MP. Diuretics and potassium/magnesium depletion. Directions for treatment. Am J Med 1987;82:38-47.. PubMed
- Hollifield JW. Magnesium depletion, diuretics, and arrhythmias. Am J Med 1987;82:30-7.. PubMed
- Heidenreich O. Mode of action of conventional and potassium-sparing diuretics--aspects with relevance to Mg-sparing effects. Magnesium 1984;3:248-56..
- Pfaffenrath V, Wessely P, Meyer C, et al. Magnesium in the prophylaxis of migraine--a double-blind placebo-controlled study. Cephalalgia 1996;16:436-40.. PubMed
- Wang F, Van Den Eeden SK, Ackerson LM, et al. Oral magnesium oxide prophylaxis of frequent migrainous headache in children: a randomized, double-blind, placebo-controlled trial. Headache 2003;43:601-10.. PubMed
- Sompolinsky D, Samra Z. Influence of magnesium and manganese on some biological and physical properties of tetracycline. J Bacteriol 1972;110:468-76.. PubMed
- Jeyabalan A, Caritis SN. Pharmacologic inhibition of preterm labor. Clin Obstet Gynecol 2002;45:99-113. PubMed
- Mittendorf R, Dambrosia J, Pryde PG, et al. Association between the use of antenatal magnesium sulfate in preterm labor and adverse health outcomes in infants. Am J Obstet Gynecol 2002;186:1111-8.. PubMed
- Witlin AG, Sibai BM. Magnesium sulfate therapy in preeclampsia and eclampsia. Obstet Gynecol 1998;92:883-9.. DOI
- Crowther CA, Hiller JE, Doyle LW. Magnesium sulphate for preventing preterm birth in threatened preterm labour. Cochrane Database Syst Rev 2002;4:CD001060. . PubMed
- Davey MJ, Teubner D. A randomized controlled trial of magnesium sulfate, in addition to usual care, for rate control in atrial fibrillation. Ann Emerg Med 2005;45:347-53.. PubMed
- L'Hommedieu CS, Nicholas D, Armes DA, et al. Potentiation of magnesium sulfate--induced neuromuscular weakness by gentamicin, tobramycin, and amikacin. J Pediatr 1983;102:629-31..
- Dunn CJ, Goa KL. Risedronate: a review of its pharmacological properties and clinical use in resorptive bone disease. Drugs 2001;61:685-712..
- Kass L, Weekes J, Carpenter L. Effect of magnesium supplementation on blood pressure: a meta-analysis. Eur J Clin Nutr 2012;66:411-8. PubMed
- Koontz SL, Friedman SA, Schwartz ML. Symptomatic hypocalcemia after tocolytic therapy with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 2004;190(6):1773-6. PubMed
- Snyder SW, Cardwell MS. Neuromuscular blockade with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 1989;161(1):35-6. PubMed
- Waisman GD, Mayorga LM, Cámera MI, et al. Magnesium plus nifedipine: potentiation of hypotensive effect in preeclampsia? Am J Obstet Gynecol. 1988;159(2):308-9. PubMed
- Brown DD, Juhl RP. Decreased bioavailability of digoxin due to antacids and kaolin-pectin. N Engl J Med. 1976;295(19):1034-7. PubMed
- Allen MD, Greenblatt DJ, Harmatz JS, et al. Effect of magnesium--aluminum hydroxide and kaolin--pectin on absorption of digoxin from tablets and capsules. J Clin Pharmacol. 1981;21(1):26-30. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an in vitro study. Thromb Haemost. 1996;76(1):88-93. DOI
- Ravn HB, Kristensen SD, Vissinger H, et al. Magnesium inhibits human platelets. Blood Coagul Fibrinolysis. 1996;7(2):241-4. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an infusion study in healthy volunteers. Thromb Haemost. 1996;75(6):939-44. DOI
- Neuvonen PJ, Kivistö KT. The effects of magnesium hydroxide on the absorption and efficacy of two glibenclamide preparations. Br J Clin Pharmacol. 1991;32(2):215-20. PubMed
- Kivistö KT, Neuvonen PJ. Enhancement of absorption and effect of glipizide by magnesium hydroxide. Clin Pharmacol Ther. 1991;49(1):39-43. PubMed
- Neuvonen PJ, Kivistö KT. Enhancement of drug absorption by antacids. An unrecognised drug interaction. Clin Pharmacokinet. 1994;27(2):120-8. PubMed
- Shechter, M., Merz, C. N., Paul-Labrador, M., Meisel, S. R., Rude, R. K., Molloy, M. D., Dwyer, J. H., Shah, P. K., and Kaul, S. Beneficial antithrombotic effects of the association of pharmacological oral magnesium therapy with aspirin in coronary heart
- Ganzevoort, J. W., Hoogerwaard, E. M., and van der Post, J. A. [Hypocalcemic delirium due to magnesium sulphate therapy in a pregnant woman with pre-eclampsia]. Ned.Tijdschr.Geneeskd. 8-3-2002;146(31):1453-1456.
- Horner, S. M. Efficacy of intravenous magnesium in acute myocardial infarction in reducing arrhythmias and mortality. Meta-analysis of magnesium in acute myocardial infarction. Circulation 1992;86(3):774-779. PubMed
- Azria, E., Tsatsaris, V., Goffinet, F., Kayem, G., Mignon, A., and Cabrol, D. [Magnesium sulfate in obstetrics: current data]. J Gynecol.Obstet.Biol.Reprod.(Paris) 2004;33(6 Pt 1):510-517.
- Magee, L. A., Miremadi, S., Li, J., Cheng, C., Ensom, M. H., Carleton, B., Cote, A. M., and von Dadelszen, P. Therapy with both magnesium sulfate and nifedipine does not increase the risk of serious magnesium-related maternal side effects in women with p
- Henyan, N. N., Gillespie, E. L., White, C. M., Kluger, J., and Coleman, C. I. Impact of intravenous magnesium on post-cardiothoracic surgery atrial fibrillation and length of hospital stay: a meta-analysis. Ann.Thorac.Surg. 2005;80(6):2402-2406. PubMed
- Li, J., Zhang, Q., Zhang, M., and Egger, M. Intravenous magnesium for acute myocardial infarction. Cochrane.Database.Syst.Rev. 2007;(2):CD002755. PubMed
- Doyle, L. W., Crowther, C. A., Middleton, P., Marret, S., and Rouse, D. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane.Database.Syst.Rev. 2009;(1):CD004661. PubMed
- Han, S., Crowther, C. A., and Moore, V. Magnesium maintenance therapy for preventing preterm birth after threatened preterm labour. Cochrane.Database.Syst.Rev. 2010;(7):CD000940. PubMed
- Duley, L., Gulmezoglu, A. M., Henderson-Smart, D. J., and Chou, D. Magnesium sulphate and other anticonvulsants for women with pre-eclampsia. Cochrane.Database.Syst.Rev. 2010;(11):CD000025. PubMed
- Conde-Agudelo, A., Romero, R., and Kusanovic, J. P. Nifedipine in the management of preterm labor: a systematic review and metaanalysis. Am J Obstet.Gynecol. 2011;204(2):134-20. PubMed
- Wong, G. K., Boet, R., Poon, W. S., Chan, M. T., Gin, T., Ng, S. C., and Zee, B. C. Intravenous magnesium sulphate for aneurysmal subarachnoid hemorrhage: an updated systemic review and meta-analysis. Crit Care 2011;15(1):R52. PubMed
- Magee, L., Sawchuck, D., Synnes, A., and von, Dadelszen P. SOGC Clinical Practice Guideline. Magnesium sulphate for fetal neuroprotection. J Obstet.Gynaecol.Can. 2011;33(5):516-529.
- Doyle, L. W. Antenatal magnesium sulfate and neuroprotection. Curr Opin Pediatr 2012;24(2):154-159. PubMed
- McDonald, S. D., Lutsiv, O., Dzaja, N., and Duley, L. A systematic review of maternal and infant outcomes following magnesium sulfate for pre-eclampsia/eclampsia in real-world use. Int J Gynaecol.Obstet. 2012;118(2):90-96. PubMed
- Gordon, M., Naidoo, K., Akobeng, A. K., and Thomas, A. G. Osmotic and stimulant laxatives for the management of childhood constipation. Cochrane.Database.Syst.Rev. 2012;7:CD009118. PubMed
- Dodd, J. M., Crowther, C. A., and Middleton, P. Oral betamimetics for maintenance therapy after threatened preterm labour. Cochrane.Database.Syst.Rev. 2012;12:CD003927. PubMed
- Wu, X., Wang, C., Zhu, J., Zhang, C., Zhang, Y., and Gao, Y. Meta-analysis of randomized controlled trials on magnesium in addition to beta-blocker for prevention of postoperative atrial arrhythmias after coronary artery bypass grafting. BMC.Cardiovasc.D PubMed
- Thorp, J. M., Jr., Katz, V. L., Campbell, D., and Cefalo, R. C. Hypersensitivity to magnesium sulfate. Am.J.Obstet.Gynecol. 1989;161(4):889-890. PubMed
- Duley L and Gulmezoglu AM. Magnesium sulphate versus lytic cocktail for eclampsia. Cochrane Database of Systematic Reviews 2000;(3) PubMed
- Gibbins KJ, Browning KR, Lopes VV, Anderson BL, Rouse DJ. Evaluation of the clinical use of magnesium sulfate for cerebral palsy prevention. Obstet Gynecol 2013;121(2 Pt 1):235-40. PubMed
- Ji D. Oral magnesium sulfate causes perforation during bowel preparation for fiberoptic colonoscopy in patients with colorectal cancer. J Emerg Med 2012;43(4):716-7. PubMed
- Yagi T, Naito T, Mino Y, Umemura K, Kawakami J. Impact of concomitant antacid administration on gabapentin plasma exposure and oral bioavailability in healthy adult subjects. Drug Metab Pharmacokinet 2012;27(2):248-54. PubMed
- Yamasaki M, Funakoshi S, Matsuda S, Imazu T, Takeda Y, Murakami T, Maeda Y. Interaction of magnesium oxide with gastric acid secretion inhibitors in clinical pharmacotherapy. Eur J Clin Pharmacol 2014;70(8):921-4. PubMed
- Choi ES, Jeong WJ, Ahn SH, Oh AY, Jeon YT, Do SH. Magnesium sulfate accelerates the onset of low-dose rocuronium in patients undergoing laryngeal microsurgery. J Clin Anesth. 2017 Feb;36:102-106. PubMed
- Ikee R, Toyoyama T, Endo T, Tsunoda M, Hashimoto N. Impact of sevelamer hydrochloride on serum magnesium concentrations in hemodialysis patients. Magnes Res. 2016 Apr 1;29(4):184-90. PubMed
- Miller ES, Sakowicz A, Leger E. Lange E, Yee LM. The association between receipt of intrapartum magnesium and postpartum hemorrhage. Am J Obstet Gynecol 2018;218(1 Suppl):S165.
- Rodríguez-Rubio L, Solis Garcia Del Pozo J, Nava E, Jordán J. Interaction between magnesium sulfate and neuromuscular blockers during the perioperative period. A systematic review and meta-analysis. J Clin Anesth. 2016;34:524-34. PubMed
- Brown RS. Magnesium Sulfate: Another Cause of a Solute Diuresis. Am J Kidney Dis. 2017;69(4):550-551. PubMed
- Park H, Qin R, Smith TJ, et al. North Central Cancer Treatment Group N10C2 (Alliance): a double-blind placebo-controlled study of magnesium supplements to reduce menopausal hot flashes. Menopause. 2015;22(6):627-32. PubMed
- Sakanoue M, Sanada J, Kanekura T. Skin eruption elicited by magnesium oxide (Maglax). J Dermatol. 2016;43(2):221-2.
- Iwamuro M, Saito S, Yoshioka M, et al. A Magnesium Oxide Bezoar. Intern Med. 2018;57(21):3087-3091. PubMed
- Vilchez G, Dai J, Kumar K, Mundy D, Kontopoulos E, Sokol RJ. Racial/ethnic disparities in magnesium sulfate neuroprotection: a subgroup analysis of a multicenter randomized controlled trial. J Matern Fetal Neonatal Med. 2018;31(17):2304-2311. PubMed
- Drug Safety Communication: FDA Recommends Against Prolonged Use of Magnesium Sulfate to Stop Pre-term Labor Due to Bone Changes in Exposed Babies. U.S. Food and Drug Administration (FDA), May 30, 2013. https://www.fda.gov/downloads/Drugs/DrugSafety/UCM353
- Committee Opinion: Magnesium Sulfate Use in Obstetrics. The American College of Obstetricians and Gynecologists Committee on Obstetric Practice Society for Maternal-Fetal Medicine, Number 652, January 2016. https://www.acog.org/Clinical-Guidance-and-Publi
- Kashihara Y, Terao Y, Yoda K, et al. Effects of magnesium oxide on pharmacokinetics of L-dopa/carbidopa and assessment of pharmacodynamic changes by a model-based simulation. Eur J Clin Pharmacol. 2019;75(3):351-361. PubMed
- Shepherd E, Salam RA, Manhas D, et al. Antenatal magnesium sulphate and adverse neonatal outcomes: A systematic review and meta-analysis. PLoS Med. 2019;16(12):e1002988. PubMed
- Hong JY, Hong JY, Choi YS, et al. Antenatal magnesium sulfate treatment and risk of necrotizing enterocolitis in preterm infants born at less than 32 weeks of gestation. Sci Rep. 2020;10(1):12826. PubMed
- Schuh S, Sweeney J, Rumantir M, et al. Effect of nebulized magnesium vs placebo added to albuterol on hospitalization among children with refractory acute asthma treated in the emergency department: a randomized clinical trial. JAMA. 2020;324(20):2038-20 PubMed
- Almeida CED, Carvalho LR, Andrade CVC, Nascimento PD Jr, Barros GAM, Modolo NSP. Effects of magnesium sulphate on the onset time of rocuronium at different doses: a randomized clinical trial. Braz J Anesthesiol. 2021;71(5):482-8. PubMed
- Gochi Valdovinos A, Arriaga-Redondo M, Dejuan Bitriá E, Pérez Rodríguez I, Márquez Isidro E, Blanco Bravo D. Prenatal therapy with magnesium sulphate and intestinal obstruction due to meconium in preterm newborns. An Pediatr (Engl Ed). 2022 Feb;96(2):138- PubMed
- Iio K, Kondo E, Shibata E, et al. Long-term tocolysis with magnesium sulfate as a risk factor for low bone mass: a case series. J Med Cases. 2022 Feb;13(2):47-50. PubMed
- Eiraku K, Uozumi Y, Hieda M, Maruyama T, Nomura H. A senile case of heart failure associated with hypermagnesemia induced by magnesium-containing laxative agent. Geriatr Gerontol Int. 2022;22(10):897-899.
- Enayati A, Gin JH, Sajeev JK, et al. Efficacy of intravenous magnesium for the management of non-post operative atrial fibrillation with rapid ventricular response: A systematic review and meta-analysis. J Cardiovasc Electrophysiol 2023;34(5):1286-1295. PubMed
- Su YH, Luo DC, Pang Y. Effects of intraoperative Magnesium sulfate infusion on emergency agitation during general anesthesia in patients undergoing radical mastectomy: a randomized controlled study. BMC Anesthesiol 2023;23(1):326. PubMed
- Han J, Park HY, Shin HJ, Chung SH, Do SH. Effects of magnesium sulphate on neostigmine-induced recovery from moderate neuromuscular blockade with rocuronium: a randomized controlled trial. Magnes Res 2023;36(2):31-39. PubMed
- Lee AT, Cordova JC, Jamplis RP, Pomicter GR. Posterior Reversible Encephalopathy Syndrome and Eclampsia in the Setting of Magnesium Toxicity: A Case Report. A A Pract 2023;17(11):e01726. PubMed
- Darmawan D, Rengganis I, Rumende CM, et al. Effectiveness and Safety of Nebulized Magnesium as Last Line Treatment in Adults with Acute Asthma Attack: A Systematic Review and Meta-Analysis. Acta Med Indones 2024;56(1):3-12.
- Shepherd ES, Goldsmith S, Doyle LW, et al. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane Database Syst Rev 2024;5(5):CD004661. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Oriental Arborvitae 2 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC