
RePlenish Ingredients & Drug Interactions
by Zemvelo
What is this page for?
First and foremost: checking RePlenish against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
RePlenish is a dietary supplement by Zemvelo with 5 active ingredients. Its ingredients are commonly taken for replacing fluids and electrolytes, preventing dehydration during exercise or illness, treating low blood sodium (under medical care).Based on those ingredients, 467 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Magnesium, Sodium, Potassium. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against RePlenish by Zemvelo
Ask about any prescription or over-the-counter medication and we check it for interactions with RePlenish by Zemvelo — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of RePlenish by Zemvelo
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
RePlenish is a 5-ingredient electrolyte liquid. The three active electrolytes are sodium, potassium, and magnesium — the main minerals your body needs to balance fluid, nerve signals, and muscle work.
The product also contains chloride and trace minerals as active ingredients. Inactive ingredients are water, CHD-FA fulvic acid, and sorbic acid (a preservative).
Does it work?
Strong evidence
Sodium has established uses: it's rated likely effective for cystic fibrosis and possibly effective for amphotericin B kidney damage. The data on file doesn't have effectiveness ratings for potassium.
Magnesium is effective for dyspepsia (indigestion), constipation, magnesium deficiency (hypomagnesemia), and prevention of pre-eclampsia in pregnancy. We hold no effectiveness ratings for chloride or trace minerals.
How safe is it?
Well-documented data
Sodium is well tolerated in normal dietary amounts, but the safety notes warn against supplements or high intake without medical advice — too much is linked to high blood pressure and heart strain. Potassium from food is safe; supplements can cause dangerously high blood levels, especially in people with kidney disease.
Magnesium is generally safe for healthy adults at recommended amounts. In pregnancy, magnesium is rated possibly unsafe at high doses; the safety notes say to use supplements only under a doctor's guidance.
Common side effects of magnesium include diarrhea, nausea, and vomiting. Rare serious effects of sodium include worsening heart and kidney disease; rare serious potassium effects include heart rhythm problems and cardiac arrest.
Meds to double-check
Major interaction found
Check your medications against these types before taking this product: levodopa/carbidopa (Parkinson's) — the most serious; blood pressure drugs (antihypertensives, ACE inhibitors, ARBs, calcium channel blockers); potassium-sparing diuretics and other water pills; lithium; corticosteroids; skeletal muscle relaxants; quinolone and other antibiotics; bisphosphonates; sulfonylurea diabetes drugs; and antacids. Use the medication search tool on this page with your exact drug names.
The bottom line
Scorecard at a glanceFully disclosed formula with clinical evidence supporting its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
RePlenish is an electrolyte replacement for dehydration or mineral loss, especially useful if you have cystic fibrosis or are recovering from certain infections. If you take blood pressure drugs, lithium, Parkinson's medication, diuretics, or antibiotics, check your exact medications with the tool before starting — several of these can interact.
Talk to your pharmacist or doctor, especially if you have kidney disease, heart disease, or are pregnant.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 3 of 5 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jul 24, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about RePlenish, straight from the product label.
| Brand | Zemvelo |
|---|---|
| Barcode (UPC) | 891663002032 |
| Net contents | 4 Fluid Ounce(s); 120 mL |
| Market status | On market |
| Date entered into DSLD | Jul 24, 2025 |
| DSLD ID | 333502 |
| Product type | Mineral |
| Supplement form | Liquid |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Children 4 or More Years of Age, Vegan, Vegetarian, Adult (18 - 50 Years), Gluten Free, Dairy Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
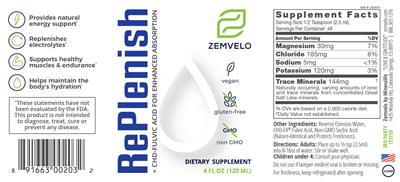
Supplement Facts
The label details for RePlenish by Zemvelo, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Sodium | 5 mg | 1% |
| Potassium | 120 mg | 3% |
| Magnesium | 30 mg | 7% |
| Chloride | 185 mg | 8% |
| Trace Minerals | 144 mg | -- |
Other ingredients: Water, CHD-FA Fulvic Acid, Sorbic Acid
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formulation
Provides natural energy support Replenishes electrolytes Supports healthy muscles & endurance Helps maintain the body’s hydration
Vegan
Gluten-free Non GMO
3rd Party Tested cGMP
FDA Disclaimer Statement
These statements have not been evaluated by the FDA. This product is not intended to diagnose, treat, cure or prevent any disease.
Formula
RePlenish + CHD-Fulvic Acid for Enhanced Absorption
FDA Statement of Identity
Dietary Supplement
Suggested/Recommended/Usage/Directions
Directions: Adults: Place up to 1/2 tsp (2.5 ml) into 8–16 oz of water. Stir or shake well.
Precautions
Children under 4: Consult your physician.
Do not use if tamper evident seal is broken or missing.
Storage
For freshness, keep refrigerated after opening.
General Statements
"Love & gratitude"
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
RePlenish by Zemvelo label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in RePlenish by Zemvelo
These are the 5 active ingredients this product is made of. Select any to open its full monograph.
Serving size2.5 mL Dosage formLiquid Servings per container48 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Sodium
Interacts with205 drugs
Sodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets g...
Sodium monograph & interactionsPotassium
Interacts with62 drugs
Potassium is an essential mineral your body needs for nerve signals, muscle function, and a steady heartbeat, and most people get enough from a balanc...
Potassium monograph & interactionsMagnesium
Interacts with295 drugs
Magnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preven...
Magnesium monograph & interactionsChloride
Trace Minerals
Other (inactive) ingredients: Water, CHD-FA Fulvic Acid, Sorbic Acid. These complete the product’s ingredient list but are not active constituents.
RePlenish by Zemvelo Drug Interactions
HelloPharmacist Interaction Report
RePlenish by Zemvelo contains sodium, potassium, and magnesium — all electrolytes that interact with a number of medications.
The most serious is magnesium with levodopa/carbidopa (Sinemet), a Parkinson's drug: magnesium can cut the drug's effectiveness by about a third, which matters when you're managing tremor and stiffness.
Read the full breakdown — every affected drug type, severity by severity
Sodium poses Moderate-level risks with blood pressure medications (antihypertensives), heart and kidney drugs, lithium for bipolar disorder, corticosteroids, and HIV medication (didanosine). High sodium intake can blunt blood pressure control and, with lithium, tip levels toward toxicity.
Potassium carries Moderate risks with three major classes: potassium-sparing water pills, ACE inhibitors, and ARB blood pressure drugs — all can trap potassium in your body, raising it to dangerous levels. Magnesium additionally interacts with muscle relaxants, certain antibiotics (quinolones and bisphosphonates for bone), diabetes drugs (sulfonylureas), antacids, and calcium channel blockers for blood pressure.
We could not check Chloride or Trace Minerals — no interaction data is on file for them. Altogether, these interactions span 463 individual medications.
Before you start, search your exact medications in the tool on this page.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against RePlenish?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in RePlenish interact with 467 drugs. Click any drug to see the details.
3 of the 5 ingredients in RePlenish interact with drugs. Each result below shows which ingredient is responsible. Magnesium Sodium Potassium
Benserazide, LevodopaMadopar, Prolopa
How Benserazide, Levodopa interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Benserazide, Levodopa interactionCarbidopaLodosyn
How Carbidopa interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa interactionCarbidopa, LevodopaDhivy, Rytary, Sinemet, Sinemet CR
How Carbidopa, Levodopa interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa, Levodopa interactionCarbidopa, Levodopa, EntacaponeStalevo
How Carbidopa, Levodopa, Entacapone interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa, Levodopa, Entacapone interactionLevodopaInbrija, Larodopa
How Levodopa interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Levodopa interactionLevodopa, CarbidopaDuodopa
How Levodopa, Carbidopa interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Levodopa, Carbidopa interactionAcebutololRhotral, Sectral
How Acebutolol interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Acebutolol interactionAcetaminophen, ChlorzoxazoneAcetazone Forte, Extra Strength Tylenol Aches & Strains, Parafon Forte
How Acetaminophen, Chlorzoxazone interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Acetaminophen, Chlorzoxazone interactionAcetaminophen, Chlorzoxazone, CodeineAcetazone Forte C8, Parafon Forte C8
How Acetaminophen, Chlorzoxazone, Codeine interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Acetaminophen, Chlorzoxazone, Codeine interactionAcetaminophen, Codeine, MethocarbamolAcetaminophen, Codeine, Methocarbamol, Robaxacet 8
How Acetaminophen, Codeine, Methocarbamol interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Acetaminophen, Codeine, Methocarbamol interactionAcetaminophen, MethocarbamolRobaxacet
How Acetaminophen, Methocarbamol interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Acetaminophen, Methocarbamol interactionAcetaminophen, OrphenadrineOrfenagesic
How Acetaminophen, Orphenadrine interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Acetaminophen, Orphenadrine interactionAcetazolamideAk-Zol, Diamox
How Acetazolamide interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Acetazolamide interactionAcetohexamideDymelor
How Acetohexamide interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumSulfonylureas Moderate
Interaction Summary
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Read the full Magnesium + Acetohexamide interactionAlcuroniumAlcuronium
How Alcuronium interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Alcuronium interactionAlendronateBinosto, Fosamax
How Alendronate interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumBisphosphonates Moderate
Interaction Summary
Magnesium can decrease absorption of bisphosphonates.
Read the full Magnesium + Alendronate interactionAlendronate Sodium
How Alendronate Sodium interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumBisphosphonates Moderate
Interaction Summary
Magnesium can decrease absorption of bisphosphonates.
Read the full Magnesium + Alendronate Sodium interactionAlendronate Sodium, CholecalciferolFosamax Plus D
How Alendronate Sodium, Cholecalciferol interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumBisphosphonates Moderate
Interaction Summary
Magnesium can decrease absorption of bisphosphonates.
Read the full Magnesium + Alendronate Sodium, Cholecalciferol interactionAlginic Acid, Aluminum HydroxideRafton
How Alginic Acid, Aluminum Hydroxide interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumAntacids Moderate
Interaction Summary
Use of acid reducers may reduce the laxative effect of magnesium oxide.
Read the full Magnesium + Alginic Acid, Aluminum Hydroxide interactionAliskirenTekturna
How Aliskiren interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Aliskiren interactionAluminum HydroxideAlu-Cap, Amphojel, Gaviscon
How Aluminum Hydroxide interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumAntacids Moderate
Interaction Summary
Use of acid reducers may reduce the laxative effect of magnesium oxide.
Read the full Magnesium + Aluminum Hydroxide interactionAluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium HydroxideAscriptin Codeine #2
How Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumAntacids, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Use of acid reducers may reduce the laxative effect of magnesium oxide.
Read the full Magnesium + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionAluminum Hydroxide, Aspirin, Magnesium HydroxideAscriptin
How Aluminum Hydroxide, Aspirin, Magnesium Hydroxide interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumAnticoagulant/antiplatelet Drugs, Antacids Moderate
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Aluminum Hydroxide, Aspirin, Magnesium Hydroxide interactionAluminum Hydroxide, Magnesium Hydroxide (otc Drug)Maalox, Mucogel
How Aluminum Hydroxide, Magnesium Hydroxide (otc Drug) interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumAntacids Moderate
Interaction Summary
Use of acid reducers may reduce the laxative effect of magnesium oxide.
Read the full Magnesium + Aluminum Hydroxide, Magnesium Hydroxide (otc Drug) interactionAluminum Hydroxide, Magnesium Hydroxide, Simethicone (otc Drug)Mylanta
How Aluminum Hydroxide, Magnesium Hydroxide, Simethicone (otc Drug) interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumAntacids Moderate
Interaction Summary
Use of acid reducers may reduce the laxative effect of magnesium oxide.
Read the full Magnesium + Aluminum Hydroxide, Magnesium Hydroxide, Simethicone (otc Drug) interactionAluminum, Magnesium (otc Drug)Almagel
How Aluminum, Magnesium (otc Drug) interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumAntacids Moderate
Interaction Summary
Use of acid reducers may reduce the laxative effect of magnesium oxide.
Read the full Magnesium + Aluminum, Magnesium (otc Drug) interactionAmbrisentanLetairis, Volibris
How Ambrisentan interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Ambrisentan interactionAmikacinAmikin, Arikayce
How Amikacin interacts with RePlenish — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumAminoglycoside Antibiotics Moderate
Interaction Summary
Concomitant use of aminoglycoside antibiotics and magnesium can increase the risk for neuromuscular weakness.
Read the full Magnesium + Amikacin interactionAmilorideAmilamont, Midamor
How Amiloride interacts with RePlenish — through 3 ingredients. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Amiloride interactionPotassiumPotassium-sparing Diuretics Moderate
Interaction Summary
Concomitant use increases the risk of hyperkalemia.
Read the full Potassium + Amiloride interactionMagnesiumPotassium-sparing Diuretics Moderate
Interaction Summary
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Read the full Magnesium + Amiloride interactionAmiloride, HydrochlorothiazideAmil-Co, Amilzide, Moduret 25, Moduretic
How Amiloride, Hydrochlorothiazide interacts with RePlenish — through 3 ingredients. Tap an ingredient for the detail:
PotassiumPotassium-sparing Diuretics Moderate
Interaction Summary
Concomitant use increases the risk of hyperkalemia.
Read the full Potassium + Amiloride, Hydrochlorothiazide interactionMagnesiumPotassium-sparing Diuretics Moderate
Interaction Summary
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Read the full Magnesium + Amiloride, Hydrochlorothiazide interactionSodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Amiloride, Hydrochlorothiazide interactionEach ingredient & the kinds of drugs it affects
For each ingredient in RePlenish with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Magnesium
Levodopa/Carbidopa (Sinemet)
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Clinical research in healthy volunteers shows that taking magnesium oxide 1000 mg with levodopa 100 mg/carbidopa 10 mg reduces the area under the curve (AUC) of levodopa by 35% and of carbidopa by 81%. In vitro and animal research shows that magnesium produces an alkaline environment in the digestive tract, which might lead to degradation and reduced bioavailability of levodopa/carbidopa.
Aminoglycoside Antibiotics
Concomitant use of aminoglycoside antibiotics and magnesium can increase the risk for neuromuscular weakness.
Both aminoglycosides and magnesium reduce presynaptic acetylcholine release, which can lead to neuromuscular blockade and possible paralysis. This is most likely to occur with high doses of magnesium given intravenously.
Antacids
Use of acid reducers may reduce the laxative effect of magnesium oxide.
A retrospective analysis shows that, in the presence of H2 receptor antagonists (H2RAs) or proton pump inhibitors (PPIs), a higher dose of magnesium oxide is needed for a laxative effect. This may also occur with antacids. Under acidic conditions, magnesium oxide is converted to magnesium chloride and then to magnesium bicarbonate, which has an osmotic laxative effect. By reducing acidity, antacids may reduce the conversion of magnesium oxide to the active bicarbonate salt.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after magnesium containing products.
Bisphosphonates
Magnesium can decrease absorption of bisphosphonates.
Cations, including magnesium, can decrease bisphosphonate absorption. Advise patients to separate doses of magnesium and these drugs by at least 2 hours.
Calcium Channel Blockers
Magnesium can have additive effects with calcium channel blockers, although evidence is conflicting.
Magnesium inhibits calcium entry into smooth muscle cells and may therefore have additive effects with calcium channel blockers. Severe hypotension and neuromuscular blockades may occur when nifedipine is used with intravenous magnesium, although some contradictory evidence suggests that concurrent use of magnesium with nifedipine does not increase the risk of neuromuscular weakness. High doses of magnesium could theoretically have additive effects with other calcium channel blockers.
Digoxin
Magnesium salts may reduce absorption of digoxin.
Clinical evidence suggests that treatment with oral magnesium hydroxide or magnesium trisilicate reduces absorption of digoxin from the intestines. This may reduce the blood levels of digoxin and decrease its therapeutic effects.
Potassium-Sparing Diuretics
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Potassium-sparing diuretics also have magnesium-sparing properties, which can counteract the magnesium losses associated with loop and thiazide diuretics. Theoretically, increased magnesium levels could result from concomitant use of potassium-sparing diuretics and magnesium supplements.
Quinolone Antibiotics
Magnesium decreases absorption of quinolones.
Magnesium can form insoluble complexes with quinolones and decrease their absorption. Advise patients to take these drugs at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Skeletal Muscle Relaxants
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Parenteral magnesium shortens the time to onset of skeletal muscle relaxants by about 1 minute and prolongs the duration of action by about 2 minutes. Magnesium potentiates the effects of skeletal muscle relaxants by decreasing calcium-mediated release of acetylcholine from presynaptic nerve terminals, reducing postsynaptic sensitivity to acetylcholine, and having a direct effect on the membrane potential of myocytes. Magnesium also has vasodilatory actions and increases cardiac output, allowing a greater amount of muscle relaxant to reach the motor end plate. A clinical study found that low-dose rocuronium (0.45 mg/kg), when given after administration of magnesium 30 mg/kg over 10 minutes, has an accelerated onset of effect, which matches the onset of effect seen with a full-dose rocuronium regimen (0.6 mg/kg). In another clinical study, onset times for rocuronium doses of 0.3, 0.6, and 1.2 mg/kg were 86, 76, and 50 seconds, respectively, when given alone, but were reduced to 66, 44, and 38 seconds, respectively, when the doses were given after a 15-minute infusion of magnesium sulfate 60 mg/kg. Giving intraoperative intravenous magnesium sulfate, 50 mg/kg loading dose followed by 15 mg/kg/hour, reduces the onset time of rocuronium, enhances its clinical effects, reduces the dose of intraoperative opiates, and prolongs the spontaneous recovery time. It does not affect the activity of subsequently administered neostigmine.
Sulfonylureas
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Clinical research shows that administration of magnesium hydroxide with glyburide increases glyburide absorption, increases maximal insulin response by 35-fold, and increases the risk of hypoglycemia, when compared with glyburide alone. A similar interaction occurs between magnesium hydroxide and glipizide. The mechanism of this effect appears to be related to the elevation of gastrointestinal pH by magnesium-based antacids, increasing solubility and enhancing absorption of sulfonylureas.
Tetracycline Antibiotics
Magnesium decreases absorption of tetracyclines.
Magnesium can form insoluble complexes with tetracyclines in the gut and decrease their absorption and antibacterial activity. Advise patients to take these drugs 1 hour before or 2 hours after magnesium supplements.
Anticoagulant/Antiplatelet Drugs
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
In vitro evidence shows that magnesium sulfate inhibits platelet aggregation, even at low concentrations. Some preliminary clinical evidence shows that infusion of magnesium sulfate increases bleeding time by 48% and reduces platelet activity. However, other clinical research shows that magnesium does not affect platelet aggregation, although inhibition of platelet-dependent thrombosis can occur.
Gabapentin (Neurontin)
Gabapentin absorption can be decreased by magnesium.
Clinical research shows that giving magnesium oxide orally along with gabapentin decreases the maximum plasma concentration of gabapentin by 33%, time to maximum concentration by 36%, and area under the curve by 43%. Advise patients to take gabapentin at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Sevelamer (Renagel, Renvela)
Sevelamer may increase serum magnesium levels.
In patients on hemodialysis, sevelamer use was associated with a 0.28 mg/dL increase in serum magnesium. The mechanism of this interaction remains unclear.
Sodium
Antihypertensive Drugs
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
High intake of dietary sodium can increase systolic and diastolic blood pressure. Also, high intake of sodium may necessitate increased use of antihypertensive medications to achieve blood pressure control in some patients, such as those with chronic kidney disease.
Corticosteroids
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Mineralocorticoids and some glucocorticoids (corticosteroids) cause sodium retention. This effect is dose-related and depends on mineralocorticoid potency. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Didanosine (Videx)
Concomitant use of didanosine with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia.
Didanosine formulations contain a significant amount of sodium.
Lithium
Altering dietary intake of sodium might alter the levels and clinical effects of lithium.
High sodium intake can reduce plasma concentrations of lithium by increasing lithium excretion. Reducing sodium intake can significantly increase plasma concentrations of lithium and cause lithium toxicity in patients being treated with lithium carbonate. Stabilizing sodium intake is shown to reduce the percentage of patients with lithium level fluctuations above 0.8 mEq/L. Patients taking lithium should avoid significant alterations in their dietary intake of sodium.
Sodium Phosphates
Theoretically, concomitant use of sodium phosphate with sodium supplements might increase the risk of hypernatremia.
Use of high doses (> 45 mL in 24 hours) of sodium phosphate, such as those used for bowel cleansing before surgery, can lead to serious electrolyte disturbances, including hypernatremia. The risk of hypernatremia is highest in the elderly and people with other risk factors for electrolyte disturbances.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related complications.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium supplements or high-sodium diets, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Tolvaptan (Samsca)
Theoretically, concomitant use of tolvaptan with sodium might increase the risk of hypernatremia.
Tolvaptan is a vasopressin receptor 2 antagonist that is used to increase sodium levels in patients with hyponatremia. Patients taking tolvaptan should use caution with the use of sodium salts such as sodium chloride.
Potassium
Ace Inhibitors (Aceis)
Using ACEIs with high doses of potassium increases the risk of hyperkalemia.
ACEIs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Angiotensin Receptor Blockers (Arbs)
Using ARBs with high doses of potassium increases the risk of hyperkalemia.
ARBs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Potassium-Sparing Diuretics
Concomitant use increases the risk of hyperkalemia.
Using potassium-sparing diuretics with potassium supplements increases the risk of hyperkalemia.
Brand information
Manufacturer and brand details for RePlenish, from the product label.
Zemvelo
See all Zemvelo products- Name
- Zemvelo by MINERALIFE
- Street Address
- 1435 Woolsey Hts
- City
- Colorado Springs
- State
- CO
- ZipCode
- 80915
- Phone Number
- 8003031376
- Web Address
- zemvelo.com
RePlenish by Zemvelo: Common Questions
Does RePlenish by Zemvelo interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Is RePlenish safe to take during pregnancy?
Can I take RePlenish while breastfeeding?
What is magnesium used for in this product?
Will RePlenish cause diarrhea?
What are the trace minerals in RePlenish?
Is this product safe for someone with kidney disease?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if RePlenish is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind RePlenish’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Sodium
Interacts with 205 drugsSodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets get more than enough—often too much—from...
Read the full Sodium monograph → Herb & supplement monographPotassium
Interacts with 62 drugsPotassium is an essential mineral your body needs for nerve signals, muscle function, and a steady heartbeat, and most people get enough from a balanced diet rich in fruits and vegetables. P...
Read the full Potassium monograph → Herb & supplement monographMagnesium
Interacts with 295 drugsMagnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preventing or correcting deficiency. Some othe...
Read the full Magnesium monograph →Sources & How We Checked
RePlenish's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 132 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Sodium 38 references
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Food and Drug Administration Science Background: Safety of Sodium Phosphates Oral Solution. September 17, 2001. Available at: http://www.fda.gov/cder/drug/safety/sodiumphospate.htm
- Coton T, Mallaret C, Coilliot C, Carre D, Guisset M. Severe acute ulcerated gastritis induced by salt. Presse Med 2009;38(3):499-500. PubMed
- Frings-Meuthen P, Buehlmeier J, Baecker N, et al. High sodium chloride intake exacerbates immobilization-induced bone resorption and protein losses. J Appl Physiol 2011;111(2):537-542. PubMed
- Frings-Meuthen P, Baecker N, Heer M. Low-grade metabolic acidosis may be the cause of sodium chloride-induced exaggerated bone resorption. J Bone Miner Res 2008;23(4):517-524. PubMed
- Alam S, Johnson AG. A meta-analysis of randomised controlled trials (RCT) among healthy normotensive and essential hypertensive elderly patients to determine the effect of high salt (NaCl) diet of blood pressure. J Hum Hypertens 1999;13(6):367-74.
- Boudville N, Ward S, Benaroia M, House AA. Increased sodium intake correlates with greater use of antihypertensive agents by subjects with chronic kidney disease. Am J Hypertens 2005;18(10):1300-5. PubMed
- Bennett WM. Drug interactions and consequences of sodium restriction. Am J Clin Nutr 1997;65(2 Suppl):678S-681S. PubMed
- Okusa MD, Crystal LJ. Clinical manifestations and management of acute lithium intoxication. Am J Med 1994;97(4):383-9. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary reference intakes for water, potassium, sodium, chloride, and sulfate. Washington, DC: National Academy Press, 2005. Available at: http://www.nap.edu/openbook.php?record_id=10925. DOI
- D'Elia L, Rossi G, Ippolito R, Cappuccio FP, Strazzullo P. Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clin Nutr 2012;31(4):489-98. PubMed
- Goldsmith SR. Hyponatremia in heart failure: time for a trial. J Card Fail 2013;19(6):398-400. PubMed
- Willocks L, Brettle R, Keen J, Valentine C, Pinching AJ. Formulations of didanosine (ddI) and salt overload. Lancet 1992;339(8786):190.
- Chen L, Zhang Z, Chen W, Whelton PK, Appel LJ. Lower Sodium Intake and Risk of Headaches: Results From the Trial of Nonpharmacologic Interventions in the Elderly. Am J Public Health. 2016;106(7):1270-5. PubMed
- Cook NR, Appel LJ, Whelton PK. Lower levels of sodium intake and reduced cardiovascular risk. Circulation. 2014;129(9):981-9. PubMed
- Cook NR, Appel LJ, Whelton PK. Sodium Intake and All-Cause Mortality Over 20 Years in the Trials of Hypertension Prevention. J Am Coll Cardiol. 2016;68(15):1609-1617. PubMed
- Mente A, O'Donnell M, Rangarajan S, et al. Associations of urinary sodium excretion with cardiovascular events in individuals with and without hypertension: a pooled analysis of data from four studies. Lancet. 2016;388(10043):465-75. PubMed
- Moosavian SP, Haghighatdoost F, Surkan PJ, Azadbakht L. Salt and obesity: a systematic review and meta-analysis of observational studies. Int J Food Sci Nutr. 2017;68(3):265-277. PubMed
- O'Donnell M, Mente A, Rangarajan S, et al. Urinary sodium and potassium excretion, mortality, and cardiovascular events. N Engl J Med. 2014;371(7):612-23. DOI
- Poggio R, Gutierrez L, Matta MG, Elorriaga N, Irazola V, Rubinstein A. Daily sodium consumption and CVD mortality in the general population: systematic review and meta-analysis of prospective studies. Public Health Nutr. 2015;18(4):695-704. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Mahtani KR, Heneghan C, Onakpoya I, et al. Reduced Salt Intake for Heart Failure: A Systematic Review. JAMA Intern Med. 2018 Dec 1;178(12):1693-1700. PubMed
- Yancy CW. Sodium Restriction in Heart Failure: Too Much Uncertainty-Do the Trials. JAMA Intern Med. 2018 Dec 1;178(12):1700-1701. PubMed
- He FJ, Campbell NRC, Ma Y, MacGregor GA, Cogswell ME, Cook NR. Errors in estimating usual sodium intake by the Kawasaki formula alter its relationship with mortality: implications for public health. Int J Epidemiol. 2018;47(6):1784-1795. PubMed
- Murthy K, Ondrey GJ, Malkani N, et al. THE EFFECTS OF HYPONATREMIA ON BONE DENSITY AND FRACTURES: A SYSTEMATIC REVIEW AND META-ANALYSIS. Endocr Pract. 2019;25(4):366-378. PubMed
- Messerli FH, Hofstetter L, Syrogiannouli L, et al. Sodium intake, life expectancy, and all-cause mortality. Eur Heart J 2021;42(21):2103-2112. PubMed
- Graudal NA, Hubeck-Graudal T, Jurgens G. Effects of low sodium diet versus high sodium diet on blood pressure, renin, aldosterone, catecholamines, cholesterol, and triglyceride. Cochrane Database Syst Rev 2020;12(12):CD004022. PubMed
- Giatti S, Santos RB, Aielo AN, et al. Association of sodium with obstructive sleep apnea. The ELSA-Brasil study. Ann Am Thorac Soc 2021;18(3):502-510. PubMed
- Nan X, Lu H, Wu J, et al. The interactive association between sodium intake, alcohol consumption and hypertension among elderly in northern China: a cross-sectional study. BMC Geriatr 2021;21(1):135. PubMed
- Kyozuka H, Fukusda T, Murata T, et al. Impact of preconception sodium intake on hypertensive disorders of pregnancy: The Japan Environment and Children's study. Pregnancy Hypertens 2021;23:66-72. PubMed
- Zhao L, Ogden CL, Yang Q, et al. Association of usual sodium intake with obesity among US children and adolescents, NHANES 2009-2016. Obesity (Silver Spring) 2021;29(3):587-594. PubMed
- Ma Y, He FJ, Sun Q, et al. 24-Hour urinary sodium and potassium excretion and cardiovascular risk. N Engl J Med 2022;386(3):252-263. PubMed
- Liu J, Yang X, Zhang P, et al. Association of urinary sodium excretion and left ventricular hypertrophy in people with type 2 diabetes mellitus: A cross-sectional study. Front Endocrinol (Lausanne) 2021;12:728493. PubMed
- Filippini T, Malavolti M, Whelton PK, Vinceti M. Sodium intake and risk of hypertension: A systematic review and dose-response meta-analysis of observational cohort studies. Curr Hypertens Rep 2022;24(5):133-144. PubMed
- Wang DD, Li Y, Nguyen XT, et al. Dietary sodium and potassium intake and risk of non-fatal cardiovascular diseases: The million veteran program. Nutrients 2022;14(5):1121. PubMed
- Kwak JH, Park CH, Eun CS, et al. The associations of dietary intake of high sodium and low zinc with gastric cancer mortality: A prospective cohort study in Korea. Nutr Cancer 2022;74(10):3501-3508. PubMed
- George S, Maiti R, Mishra BR, Jena M, Mohapatra D. Effect of regulated add-on sodium chloride intake on stabilization of serum lithium concentration in bipolar disorder: A randomized controlled trial. Bipolar Disord 2023;25(1):66-75. PubMed
- Zhou TL, Schütten MTJ, Kroon AA, et al. Urinary Sodium Excretion and Salt Intake Are Not Associated With Blood Pressure Variability in a White General Population. J Am Heart Assoc 2023;12(1):e026578. PubMed
Potassium 12 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Gennaro A. Remington: The Science and Practice of Pharmacy. 19th ed. Lippincott: Williams & Wilkins, 1996.
- Whelton PK, He J, Cutler JA, et al. Effects of oral potassium on blood pressure. Meta-analysis of randomized controlled clinical trials. JAMA 1997;277:1624-32. PubMed
- Phillips, C. O., Kashani, A., Ko, D. K., Francis, G., and Krumholz, H. M. Adverse effects of combination angiotensin II receptor blockers plus angiotensin-converting enzyme inhibitors for left ventricular dysfunction: a quantitative review of data from ra DOI
- Altieri, P. I., Herrero, C., Suero, R., and Ortiz, A. Bleeding duodenal ulcer in a patient taking slow-releasing potassium tablets. Bol.Asoc.Med P.R. 1977;69(8):276.
- Raf, L. E. Enteric-coated potassium chloride tablets and ulcer of the small intestine. Acta Chir Scand Suppl 1967;(374):1-87.
- Potassium chloride oral solution [package insert]. Allentown, PA: Lehigh Valley Technologies, Inc.; 2014.
- Potassium chloride injection [package insert]. Lake Forest, IL: Hospira Inc.; 2009.
- Patel RB, Tannenbaum S, Viana-Tejedor A, et al. Serum potassium levels, cardiac arrhythmias, and mortality following non-ST-elevation myocardial infarction or unstable angina: insights from MERLIN-TIMI 36. Eur Heart J Acute Cardiovasc Care 2017 Feb;6(1):1 PubMed
- Malta D, Arcand J, Ravindran A, Floras V, Allard JP, Newton GE. Adequate intake of potassium does not cause hyperkalemia in hypertensive individuals taking medications that antagonize the renin angiotensin aldosterone system. Am J Clin Nutr 2016 Oct;104(4 PubMed
- Keskin M, Kaya A, Tatlisu MA, et al. The effect of serum potassium level on in-hospital and long-term mortality in ST elevation myocardial infarction. Int J cardiol. 2016 Oct 15;221:505-10.
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
Magnesium 82 references
- Rodin SM, Johnson BF. Pharmacokinetic interactions with digoxin. Clin Pharmacokinet 1988;15:227-44.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Dahle LO, Berg G, Hammar M, et al. The effect of oral magnesium substitution on pregnancy-induced leg cramps. Am J Obstet Gynecol 1995;173:175-80. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Peikert A, Wilimzig C, Kohne-Volland R. Prophylaxis of migraine with oral magnesium: results from a prospective, multi-center, placebo-controlled and double-blind randomized study. Cephalalgia 1996;16:257-63. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Washington, DC: National Academy Press, 1999. Available at: http://books.nap.edu/books/0309063507/html/index.html.
- Birrer RB, Shallash AJ, Totten V. Hypermagnesemia-induced fatality following epsom salt gargles. J Emerg Med 2002;22:185-8. PubMed
- Ryan MP. Diuretics and potassium/magnesium depletion. Directions for treatment. Am J Med 1987;82:38-47.. PubMed
- Hollifield JW. Magnesium depletion, diuretics, and arrhythmias. Am J Med 1987;82:30-7.. PubMed
- Heidenreich O. Mode of action of conventional and potassium-sparing diuretics--aspects with relevance to Mg-sparing effects. Magnesium 1984;3:248-56..
- Pfaffenrath V, Wessely P, Meyer C, et al. Magnesium in the prophylaxis of migraine--a double-blind placebo-controlled study. Cephalalgia 1996;16:436-40.. PubMed
- Wang F, Van Den Eeden SK, Ackerson LM, et al. Oral magnesium oxide prophylaxis of frequent migrainous headache in children: a randomized, double-blind, placebo-controlled trial. Headache 2003;43:601-10.. PubMed
- Sompolinsky D, Samra Z. Influence of magnesium and manganese on some biological and physical properties of tetracycline. J Bacteriol 1972;110:468-76.. PubMed
- Jeyabalan A, Caritis SN. Pharmacologic inhibition of preterm labor. Clin Obstet Gynecol 2002;45:99-113. PubMed
- Mittendorf R, Dambrosia J, Pryde PG, et al. Association between the use of antenatal magnesium sulfate in preterm labor and adverse health outcomes in infants. Am J Obstet Gynecol 2002;186:1111-8.. PubMed
- Witlin AG, Sibai BM. Magnesium sulfate therapy in preeclampsia and eclampsia. Obstet Gynecol 1998;92:883-9.. DOI
- Crowther CA, Hiller JE, Doyle LW. Magnesium sulphate for preventing preterm birth in threatened preterm labour. Cochrane Database Syst Rev 2002;4:CD001060. . PubMed
- Davey MJ, Teubner D. A randomized controlled trial of magnesium sulfate, in addition to usual care, for rate control in atrial fibrillation. Ann Emerg Med 2005;45:347-53.. PubMed
- L'Hommedieu CS, Nicholas D, Armes DA, et al. Potentiation of magnesium sulfate--induced neuromuscular weakness by gentamicin, tobramycin, and amikacin. J Pediatr 1983;102:629-31..
- Dunn CJ, Goa KL. Risedronate: a review of its pharmacological properties and clinical use in resorptive bone disease. Drugs 2001;61:685-712..
- Kass L, Weekes J, Carpenter L. Effect of magnesium supplementation on blood pressure: a meta-analysis. Eur J Clin Nutr 2012;66:411-8. PubMed
- Koontz SL, Friedman SA, Schwartz ML. Symptomatic hypocalcemia after tocolytic therapy with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 2004;190(6):1773-6. PubMed
- Snyder SW, Cardwell MS. Neuromuscular blockade with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 1989;161(1):35-6. PubMed
- Waisman GD, Mayorga LM, Cámera MI, et al. Magnesium plus nifedipine: potentiation of hypotensive effect in preeclampsia? Am J Obstet Gynecol. 1988;159(2):308-9. PubMed
- Brown DD, Juhl RP. Decreased bioavailability of digoxin due to antacids and kaolin-pectin. N Engl J Med. 1976;295(19):1034-7. PubMed
- Allen MD, Greenblatt DJ, Harmatz JS, et al. Effect of magnesium--aluminum hydroxide and kaolin--pectin on absorption of digoxin from tablets and capsules. J Clin Pharmacol. 1981;21(1):26-30. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an in vitro study. Thromb Haemost. 1996;76(1):88-93. DOI
- Ravn HB, Kristensen SD, Vissinger H, et al. Magnesium inhibits human platelets. Blood Coagul Fibrinolysis. 1996;7(2):241-4. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an infusion study in healthy volunteers. Thromb Haemost. 1996;75(6):939-44. DOI
- Neuvonen PJ, Kivistö KT. The effects of magnesium hydroxide on the absorption and efficacy of two glibenclamide preparations. Br J Clin Pharmacol. 1991;32(2):215-20. PubMed
- Kivistö KT, Neuvonen PJ. Enhancement of absorption and effect of glipizide by magnesium hydroxide. Clin Pharmacol Ther. 1991;49(1):39-43. PubMed
- Neuvonen PJ, Kivistö KT. Enhancement of drug absorption by antacids. An unrecognised drug interaction. Clin Pharmacokinet. 1994;27(2):120-8. PubMed
- Shechter, M., Merz, C. N., Paul-Labrador, M., Meisel, S. R., Rude, R. K., Molloy, M. D., Dwyer, J. H., Shah, P. K., and Kaul, S. Beneficial antithrombotic effects of the association of pharmacological oral magnesium therapy with aspirin in coronary heart
- Ganzevoort, J. W., Hoogerwaard, E. M., and van der Post, J. A. [Hypocalcemic delirium due to magnesium sulphate therapy in a pregnant woman with pre-eclampsia]. Ned.Tijdschr.Geneeskd. 8-3-2002;146(31):1453-1456.
- Horner, S. M. Efficacy of intravenous magnesium in acute myocardial infarction in reducing arrhythmias and mortality. Meta-analysis of magnesium in acute myocardial infarction. Circulation 1992;86(3):774-779. PubMed
- Azria, E., Tsatsaris, V., Goffinet, F., Kayem, G., Mignon, A., and Cabrol, D. [Magnesium sulfate in obstetrics: current data]. J Gynecol.Obstet.Biol.Reprod.(Paris) 2004;33(6 Pt 1):510-517.
- Magee, L. A., Miremadi, S., Li, J., Cheng, C., Ensom, M. H., Carleton, B., Cote, A. M., and von Dadelszen, P. Therapy with both magnesium sulfate and nifedipine does not increase the risk of serious magnesium-related maternal side effects in women with p
- Henyan, N. N., Gillespie, E. L., White, C. M., Kluger, J., and Coleman, C. I. Impact of intravenous magnesium on post-cardiothoracic surgery atrial fibrillation and length of hospital stay: a meta-analysis. Ann.Thorac.Surg. 2005;80(6):2402-2406. PubMed
- Li, J., Zhang, Q., Zhang, M., and Egger, M. Intravenous magnesium for acute myocardial infarction. Cochrane.Database.Syst.Rev. 2007;(2):CD002755. PubMed
- Doyle, L. W., Crowther, C. A., Middleton, P., Marret, S., and Rouse, D. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane.Database.Syst.Rev. 2009;(1):CD004661. PubMed
- Han, S., Crowther, C. A., and Moore, V. Magnesium maintenance therapy for preventing preterm birth after threatened preterm labour. Cochrane.Database.Syst.Rev. 2010;(7):CD000940. PubMed
- Duley, L., Gulmezoglu, A. M., Henderson-Smart, D. J., and Chou, D. Magnesium sulphate and other anticonvulsants for women with pre-eclampsia. Cochrane.Database.Syst.Rev. 2010;(11):CD000025. PubMed
- Conde-Agudelo, A., Romero, R., and Kusanovic, J. P. Nifedipine in the management of preterm labor: a systematic review and metaanalysis. Am J Obstet.Gynecol. 2011;204(2):134-20. PubMed
- Wong, G. K., Boet, R., Poon, W. S., Chan, M. T., Gin, T., Ng, S. C., and Zee, B. C. Intravenous magnesium sulphate for aneurysmal subarachnoid hemorrhage: an updated systemic review and meta-analysis. Crit Care 2011;15(1):R52. PubMed
- Magee, L., Sawchuck, D., Synnes, A., and von, Dadelszen P. SOGC Clinical Practice Guideline. Magnesium sulphate for fetal neuroprotection. J Obstet.Gynaecol.Can. 2011;33(5):516-529.
- Doyle, L. W. Antenatal magnesium sulfate and neuroprotection. Curr Opin Pediatr 2012;24(2):154-159. PubMed
- McDonald, S. D., Lutsiv, O., Dzaja, N., and Duley, L. A systematic review of maternal and infant outcomes following magnesium sulfate for pre-eclampsia/eclampsia in real-world use. Int J Gynaecol.Obstet. 2012;118(2):90-96. PubMed
- Gordon, M., Naidoo, K., Akobeng, A. K., and Thomas, A. G. Osmotic and stimulant laxatives for the management of childhood constipation. Cochrane.Database.Syst.Rev. 2012;7:CD009118. PubMed
- Dodd, J. M., Crowther, C. A., and Middleton, P. Oral betamimetics for maintenance therapy after threatened preterm labour. Cochrane.Database.Syst.Rev. 2012;12:CD003927. PubMed
- Wu, X., Wang, C., Zhu, J., Zhang, C., Zhang, Y., and Gao, Y. Meta-analysis of randomized controlled trials on magnesium in addition to beta-blocker for prevention of postoperative atrial arrhythmias after coronary artery bypass grafting. BMC.Cardiovasc.D PubMed
- Thorp, J. M., Jr., Katz, V. L., Campbell, D., and Cefalo, R. C. Hypersensitivity to magnesium sulfate. Am.J.Obstet.Gynecol. 1989;161(4):889-890. PubMed
- Duley L and Gulmezoglu AM. Magnesium sulphate versus lytic cocktail for eclampsia. Cochrane Database of Systematic Reviews 2000;(3) PubMed
- Gibbins KJ, Browning KR, Lopes VV, Anderson BL, Rouse DJ. Evaluation of the clinical use of magnesium sulfate for cerebral palsy prevention. Obstet Gynecol 2013;121(2 Pt 1):235-40. PubMed
- Ji D. Oral magnesium sulfate causes perforation during bowel preparation for fiberoptic colonoscopy in patients with colorectal cancer. J Emerg Med 2012;43(4):716-7. PubMed
- Yagi T, Naito T, Mino Y, Umemura K, Kawakami J. Impact of concomitant antacid administration on gabapentin plasma exposure and oral bioavailability in healthy adult subjects. Drug Metab Pharmacokinet 2012;27(2):248-54. PubMed
- Yamasaki M, Funakoshi S, Matsuda S, Imazu T, Takeda Y, Murakami T, Maeda Y. Interaction of magnesium oxide with gastric acid secretion inhibitors in clinical pharmacotherapy. Eur J Clin Pharmacol 2014;70(8):921-4. PubMed
- Choi ES, Jeong WJ, Ahn SH, Oh AY, Jeon YT, Do SH. Magnesium sulfate accelerates the onset of low-dose rocuronium in patients undergoing laryngeal microsurgery. J Clin Anesth. 2017 Feb;36:102-106. PubMed
- Ikee R, Toyoyama T, Endo T, Tsunoda M, Hashimoto N. Impact of sevelamer hydrochloride on serum magnesium concentrations in hemodialysis patients. Magnes Res. 2016 Apr 1;29(4):184-90. PubMed
- Miller ES, Sakowicz A, Leger E. Lange E, Yee LM. The association between receipt of intrapartum magnesium and postpartum hemorrhage. Am J Obstet Gynecol 2018;218(1 Suppl):S165.
- Rodríguez-Rubio L, Solis Garcia Del Pozo J, Nava E, Jordán J. Interaction between magnesium sulfate and neuromuscular blockers during the perioperative period. A systematic review and meta-analysis. J Clin Anesth. 2016;34:524-34. PubMed
- Brown RS. Magnesium Sulfate: Another Cause of a Solute Diuresis. Am J Kidney Dis. 2017;69(4):550-551. PubMed
- Park H, Qin R, Smith TJ, et al. North Central Cancer Treatment Group N10C2 (Alliance): a double-blind placebo-controlled study of magnesium supplements to reduce menopausal hot flashes. Menopause. 2015;22(6):627-32. PubMed
- Sakanoue M, Sanada J, Kanekura T. Skin eruption elicited by magnesium oxide (Maglax). J Dermatol. 2016;43(2):221-2.
- Iwamuro M, Saito S, Yoshioka M, et al. A Magnesium Oxide Bezoar. Intern Med. 2018;57(21):3087-3091. PubMed
- Vilchez G, Dai J, Kumar K, Mundy D, Kontopoulos E, Sokol RJ. Racial/ethnic disparities in magnesium sulfate neuroprotection: a subgroup analysis of a multicenter randomized controlled trial. J Matern Fetal Neonatal Med. 2018;31(17):2304-2311. PubMed
- Drug Safety Communication: FDA Recommends Against Prolonged Use of Magnesium Sulfate to Stop Pre-term Labor Due to Bone Changes in Exposed Babies. U.S. Food and Drug Administration (FDA), May 30, 2013. https://www.fda.gov/downloads/Drugs/DrugSafety/UCM353
- Committee Opinion: Magnesium Sulfate Use in Obstetrics. The American College of Obstetricians and Gynecologists Committee on Obstetric Practice Society for Maternal-Fetal Medicine, Number 652, January 2016. https://www.acog.org/Clinical-Guidance-and-Publi
- Kashihara Y, Terao Y, Yoda K, et al. Effects of magnesium oxide on pharmacokinetics of L-dopa/carbidopa and assessment of pharmacodynamic changes by a model-based simulation. Eur J Clin Pharmacol. 2019;75(3):351-361. PubMed
- Shepherd E, Salam RA, Manhas D, et al. Antenatal magnesium sulphate and adverse neonatal outcomes: A systematic review and meta-analysis. PLoS Med. 2019;16(12):e1002988. PubMed
- Hong JY, Hong JY, Choi YS, et al. Antenatal magnesium sulfate treatment and risk of necrotizing enterocolitis in preterm infants born at less than 32 weeks of gestation. Sci Rep. 2020;10(1):12826. PubMed
- Schuh S, Sweeney J, Rumantir M, et al. Effect of nebulized magnesium vs placebo added to albuterol on hospitalization among children with refractory acute asthma treated in the emergency department: a randomized clinical trial. JAMA. 2020;324(20):2038-20 PubMed
- Almeida CED, Carvalho LR, Andrade CVC, Nascimento PD Jr, Barros GAM, Modolo NSP. Effects of magnesium sulphate on the onset time of rocuronium at different doses: a randomized clinical trial. Braz J Anesthesiol. 2021;71(5):482-8. PubMed
- Gochi Valdovinos A, Arriaga-Redondo M, Dejuan Bitriá E, Pérez Rodríguez I, Márquez Isidro E, Blanco Bravo D. Prenatal therapy with magnesium sulphate and intestinal obstruction due to meconium in preterm newborns. An Pediatr (Engl Ed). 2022 Feb;96(2):138- PubMed
- Iio K, Kondo E, Shibata E, et al. Long-term tocolysis with magnesium sulfate as a risk factor for low bone mass: a case series. J Med Cases. 2022 Feb;13(2):47-50. PubMed
- Eiraku K, Uozumi Y, Hieda M, Maruyama T, Nomura H. A senile case of heart failure associated with hypermagnesemia induced by magnesium-containing laxative agent. Geriatr Gerontol Int. 2022;22(10):897-899.
- Enayati A, Gin JH, Sajeev JK, et al. Efficacy of intravenous magnesium for the management of non-post operative atrial fibrillation with rapid ventricular response: A systematic review and meta-analysis. J Cardiovasc Electrophysiol 2023;34(5):1286-1295. PubMed
- Su YH, Luo DC, Pang Y. Effects of intraoperative Magnesium sulfate infusion on emergency agitation during general anesthesia in patients undergoing radical mastectomy: a randomized controlled study. BMC Anesthesiol 2023;23(1):326. PubMed
- Han J, Park HY, Shin HJ, Chung SH, Do SH. Effects of magnesium sulphate on neostigmine-induced recovery from moderate neuromuscular blockade with rocuronium: a randomized controlled trial. Magnes Res 2023;36(2):31-39. PubMed
- Lee AT, Cordova JC, Jamplis RP, Pomicter GR. Posterior Reversible Encephalopathy Syndrome and Eclampsia in the Setting of Magnesium Toxicity: A Case Report. A A Pract 2023;17(11):e01726. PubMed
- Darmawan D, Rengganis I, Rumende CM, et al. Effectiveness and Safety of Nebulized Magnesium as Last Line Treatment in Adults with Acute Asthma Attack: A Systematic Review and Meta-Analysis. Acta Med Indones 2024;56(1):3-12.
- Shepherd ES, Goldsmith S, Doyle LW, et al. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane Database Syst Rev 2024;5(5):CD004661. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC