
Lactoferrin Gold 1.8 Ingredients & Drug Interactions
by Nikken
What is this page for?
First and foremost: checking Lactoferrin Gold 1.8 against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Lactoferrin Gold 1.8 is a dietary supplement by Nikken with 5 active ingredients. Its ingredients are commonly taken for common cold and immune support, antioxidant support, skin health and collagen formation.Based on those ingredients, 1,151 medications have a known interaction with it, the most serious rated moderate. The ingredients most likely to interact are Turmeric root extract, Vitamin C, Inulin. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Lactoferrin Gold 1.8 by Nikken
Ask about any prescription or over-the-counter medication and we check it for interactions with Lactoferrin Gold 1.8 by Nikken — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Lactoferrin Gold 1.8 by Nikken
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
Lactoferrin Gold 1.8 contains five active ingredients. Vitamin C supports immune function and is used to prevent deficiency.
Inulin is a fiber that may help with digestive health and blood sugar control. Turmeric root extract provides curcumin, traditionally used for inflammation and digestion.
Lactoferrin is an iron-binding protein found naturally in breast milk and saliva. Lecithin is a phospholipid that aids fat digestion and is derived from plant sources.
The capsule itself is made from vegetable material, and the formula also contains sodium citrate and sodium bicarbonate as inactive ingredients.
Does it work?
Strong evidence
Evidence for this product's ingredients is mixed. Vitamin C is effective for preventing vitamin C deficiency and possibly effective for anemia, atrial fibrillation, cataracts, and exercise-related respiratory infections.
Inulin is possibly effective for weight management, constipation, and diabetes control. Turmeric root extract is possibly effective for depression, high cholesterol, and hay fever symptoms.
Lactoferrin is possibly effective for sepsis and pregnancy-related low iron, but the evidence does not support it for preventing fetal or premature infant death or for a condition called necrotizing enterocolitis. Lecithin has insufficient evidence for most uses and is considered likely ineffective for Alzheimer disease.
How safe is it?
Well-documented data
Vitamin C is generally well tolerated at normal dietary amounts but can cause stomach cramps, heartburn, nausea, diarrhea, and headache—especially at doses above 2 grams daily. Very high doses may rarely cause kidney stones in susceptible people.
Inulin commonly causes bloating, gas, and diarrhea, especially at doses over 30 grams, though it is generally well tolerated at food amounts. Turmeric is safe as a food spice but concentrated supplements carry a small risk of liver damage with prolonged use (usually reversible upon stopping).
Lactoferrin is well tolerated at typical doses but higher doses (7.2 grams daily) increase constipation, diarrhea, loss of appetite, and fatigue. Lecithin may trigger allergic skin reactions in people with egg or soy allergies and can cause stomach pain and diarrhea.
For pregnancy, vitamin C in normal prenatal vitamin amounts is likely safe, but avoid high-dose supplements unless your doctor advises it. Turmeric in pregnancy is likely safe but use only under medical supervision.
Lactoferrin and lecithin are likely safe in pregnancy. During breastfeeding, the data are less clear for turmeric and lactoferrin supplements, so talk with your healthcare provider before use.
Meds to double-check
Moderate interaction found
Check with your doctor or pharmacist before taking this product if you use estrogen-based birth control or hormone replacement therapy (vitamin C may raise estrogen levels), blood thinners like warfarin (vitamin C at high doses may reduce effectiveness), chemotherapy drugs such as doxorubicin or topoisomerase inhibitors (both vitamin C and turmeric may lower drug activity), immunosuppressants like tacrolimus (turmeric may increase levels), tamoxifen or methotrexate (turmeric interactions), sulfasalazine (turmeric interaction), tramadol, levothyroxine, fluphenazine, indinavir, or diabetes medications (inulin may lower blood sugar). These are Moderate to Minor severity concerns.
No interactions are documented for the lactoferrin or lecithin in this product.
The bottom line
Scorecard at a glanceFully disclosed formula with strong clinical evidence behind its ingredients' uses. Moderate medication interactions have been identified, and safety information is well characterized.
This product combines common supplement ingredients with documented benefits for certain conditions—vitamin C for immune support, inulin for fiber, and turmeric for inflammation. However, it carries multiple Moderate interactions, chiefly between vitamin C and estrogen-based hormones, and between turmeric and chemotherapy or immunosuppressant drugs.
If you take prescription medications, especially birth control, blood thinners, cancer treatments, or diabetes drugs, check your specific medications with your doctor or pharmacist before starting this product.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 5 of 5 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jul 25, 2012.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Lactoferrin Gold 1.8, straight from the product label.
| Brand | Nikken |
|---|---|
| Barcode (UPC) | #15581 |
| Net contents | 30 Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Jul 25, 2012 |
| DSLD ID | 11260 |
| Product type | Botanical With Nutrients |
| Supplement form | Capsule |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Gluten Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
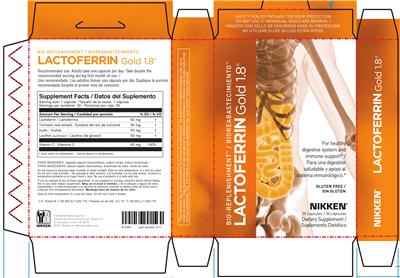
Supplement Facts
The label details for Lactoferrin Gold 1.8 by Nikken, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Vitamin C | 60 mg | 100% |
| Inulin | 50 mg | -- |
| Turmeric root extract | 30 mg | -- |
| Lactoferrin | 60 mg | -- |
| Lecithin | 50 mg | -- |
Other ingredients: vegetable capsule, Sodium Citrate, Sodium Bicarbonate
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formulation
GLUTEN FREE
Suggested/Recommended/Usage/Directions
Recommended use: Adults take one capsule per day. Take double the recommended serving during first month of use.
Storage
Do not expose to excessive heat, humidity or direct sunlight. Store at room temperature, in a cool, dry place.
Precautions
Do not use if seal is broken.
If you are allergic to any of these ingredients, or are pregnant or nursing, consult a doctor before taking this or any other dietary supplement.
Keep out of reach of children.
SAFETY SEALED PACKAGE FOR YOUR PROTECTION. DO NOT USE IF INDIVIDUAL SEALS ARE BROKEN.
Brand IP Statement(s)
U.S. Patent # 7,125,963 & 7,326,775
2011 Nikken Inc.
Bio-Replenishment
Seals/Symbols
NIKKEN
General
#15581 Last revised: 5/11
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure or prevent any disease.
General Statements
For healthy digestive system and immune support
FDA Statement of Identity
Dietary Supplement
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Lactoferrin Gold 1.8 by Nikken label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Lactoferrin Gold 1.8 by Nikken
These are the 5 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Capsule(s) Dosage formCapsule Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Vitamin C
Interacts with207 drugs
Vitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for im...
Vitamin C monograph & interactionsInulin
Interacts with86 drugs
Inulin is a type of plant fiber (a prebiotic) found naturally in foods like chicory root, onions, and garlic, and it is widely added to supplements an...
Inulin monograph & interactionsTurmeric root extract
Interacts with1,133 drugs
Turmeric is a popular spice whose main active compounds, curcuminoids, are studied mostly for inflammation and joint pain. Some research is promising,...
Turmeric root extract monograph & interactionsLactoferrin
No knowninteractions
Lactoferrin is an iron-binding protein found naturally in milk and other body fluids, and supplements are usually made from cow's milk or rice. It is...
Lactoferrin monograph & interactionsLecithin
No knowninteractions
Lecithin is a natural fatty substance found in foods and made by the body that is widely used as a supplement and food emulsifier. Evidence supporting...
Lecithin monograph & interactionsOther (inactive) ingredients: Vegetable capsule, Sodium Citrate, Sodium Bicarbonate. These complete the product’s ingredient list but are not active constituents.
Lactoferrin Gold 1.8 by Nikken Drug Interactions
HelloPharmacist Interaction Report
Lactoferrin Gold 1.8 by Nikken interacts with medications through its vitamin C, turmeric root extract, and inulin content.
The most serious interaction is vitamin C with estrogens (birth control pills and hormone replacement therapy), which can raise estrogen blood levels by up to 55% under some circumstances—a Moderate severity concern that may reduce contraceptive reliability or alter hormone therapy effects.
Read the full breakdown — every affected drug type, severity by severity
Vitamin C also has Moderate interactions with blood thinners like warfarin (high doses may reduce effectiveness), chemotherapy drugs including alkylating agents and antitumor antibiotics (antioxidant effects might lower drug activity), the antipsychotic fluphenazine, the HIV medication indinavir, thyroid medication levothyroxine, and aluminum-containing compounds. Additionally, vitamin C can increase aluminum absorption from aluminum supplements or antacids.
Turmeric root extract carries Moderate interactions with several chemotherapy and immunosuppressant drugs—topoisomerase inhibitors, antitumor antibiotics, the cancer medication tamoxifen, the immunosuppressant tacrolimus, and methotrexate. It also interacts with sulfasalazine (an anti-inflammatory), tramadol (a pain reliever), and a broad class of drugs cleared through organic anion transporters in the kidney.
Inulin has a Minor interaction with diabetes medications, theoretically increasing low blood sugar (hypoglycemia) risk, though the effect is unclear. Altogether, these interactions span 1,152 individual medications.
Lactoferrin and lecithin have no interactions documented in our data. Before starting this product, check your exact medications with the search tool on this page and discuss any concerns with your doctor or pharmacist.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Lactoferrin Gold 1.8?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Lactoferrin Gold 1.8 interact with 1,151 drugs. Click any drug to see the details.
3 of the 5 ingredients in Lactoferrin Gold 1.8 interact with drugs. Each result below shows which ingredient is responsible. Turmeric root extract Vitamin C Inulin
6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with Lactoferrin Gold 1.8 — through 1 ingredient. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with Lactoferrin Gold 1.8 — through 1 ingredient. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with Lactoferrin Gold 1.8 — through 1 ingredient. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with Lactoferrin Gold 1.8 — through 1 ingredient. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Abacavir, Lamivudine interactionAbciximabReoPro
How Abciximab interacts with Lactoferrin Gold 1.8 — through 1 ingredient. Tap an ingredient for the detail:
Turmeric Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Root Extract + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with Lactoferrin Gold 1.8 — through 1 ingredient. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Abemaciclib interactionAbiraterone
How Abiraterone interacts with Lactoferrin Gold 1.8 — through 1 ingredient. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with Lactoferrin Gold 1.8 — through 1 ingredient. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with Lactoferrin Gold 1.8 — through 1 ingredient. Tap an ingredient for the detail:
Turmeric Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Root Extract + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with Lactoferrin Gold 1.8 — through 1 ingredient. Tap an ingredient for the detail:
Turmeric Root ExtractP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
Read the full Turmeric Root Extract + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractAntidiabetes Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking turmeric with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Turmeric Root Extract + Acarbose interactionInulinAntidiabetes Drugs Minor
Interaction Summary
Theoretically, inulin might increase the risk of hypoglycemia with antidiabetes drugs.
Read the full Inulin + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Lactoferrin Gold 1.8 — through 1 ingredient. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Lactoferrin Gold 1.8 — through 1 ingredient. Tap an ingredient for the detail:
Turmeric Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Root Extract + Acenocoumarol interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Aspirin interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +2 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Aspirin, Caffeine interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, ButalbitalAxocet, Bancap, Bucet, Butex Forte, Esgic CF, Orbivan CF +5 more
How Acetaminophen, Butalbital interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Butalbital interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Butalbital, Caffeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acetaminophen, Butalbital, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Caffeine, IsomethepteneMigralam
How Acetaminophen, Caffeine, Isometheptene interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Isometheptene interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Isometheptene interactionAcetaminophen, Caffeine, PyrilamineMidol Max Strength Menstrual
How Acetaminophen, Caffeine, Pyrilamine interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Acetaminophen, Caffeine, Pyrilamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Pyrilamine interactionAcetaminophen, Chlorpheniramine Maleate, Dextromethorphan HbrVicks Formula 44M Cough, Cold & Flu Relief
How Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with Lactoferrin Gold 1.8 — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Lactoferrin Gold 1.8 with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Turmeric root extract
Alkylating Agents
Turmeric has antioxidant effects. Theoretically, this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro research suggests that curcumin, a constituent of turmeric, inhibits mechlorethamine-induced apoptosis of breast cancer cells by up to 70%. Also, animal research shows that curcumin inhibits cyclophosphamide-induced tumor regression. However, some in vitro research shows that curcumin does not affect the apoptosis capacity of etoposide. Also, other laboratory research suggests that curcumin might augment the cytotoxic effects of alkylating agents. Reasons for the discrepancies may relate to the dose of curcumin and the specific chemotherapeutic agent. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effect, if any, turmeric might have on alkylating agents.
Amlodipine (Norvasc)
Taking turmeric with amlodipine may increase levels of amlodipine.
Animal research shows that giving amlodipine 1 mg/kg as a single dose following the use of turmeric extract 200 mg/kg daily for 2 weeks increases the maximum concentration and area under the curve by 53% and 56%, respectively, when compared with amlodipine alone. Additional animal research shows that taking amlodipine 1 mg/kg with a curcumin 2 mg/kg pretreatment for 10 days increases the maximum concentration and area under the curve by about 2-fold when compared with amlodipine alone.
Anticoagulant/Antiplatelet Drugs
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs. However, research is conflicting.
Curcumin, a constituent of turmeric, has demonstrated antiplatelet effects in vitro. Furthermore, two case reports have found that taking turmeric along with warfarin or fluindione was associated with an increased international normalized ratio (INR). However, one clinical study in healthy volunteers shows that taking curcumin 500 mg daily for 3 weeks, alone or with aspirin 100 mg, does not increase antiplatelet effects or bleeding risk. It is possible that the dose of turmeric used in this study was too low to produce a notable effect.
Antidiabetes Drugs
Theoretically, taking turmeric with antidiabetes drugs might increase the risk of hypoglycemia.
Animal research and case reports suggest that curcumin, a turmeric constituent, can reduce blood glucose levels in patients with diabetes. Furthermore, clinical research in adults with type 2 diabetes shows that taking curcumin 475 mg daily for 10 days prior to taking glyburide 5 mg decreased postprandial glucose levels for up to 24 hours when compared with glyburide alone, despite the lack of a significant pharmacokinetic interaction. Other clinical studies in patients with diabetes show that taking curcumin daily can reduce blood glucose levels when compared with placebo.
Antitumor Antibiotics
Turmeric has antioxidant effects. Theoretically, this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro and animal research shows that curcumin, a constituent of turmeric, inhibits doxorubicin-induced apoptosis of breast cancer cells by up to 65%. However, curcumin does not seem to affect the apoptosis capacity of daunorubicin. In fact, some research shows that curcumin might augment the cytotoxic effects of antitumor antibiotics, increasing their effectiveness. Reasons for the discrepancies may relate to the dose of curcumin and the chemotherapeutic agent. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effects, if any, antioxidants such as turmeric have on antitumor antibiotics.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
In vitro and animal research show that turmeric and its constituents curcumin and curcuminoids inhibit CYP3A4. Also, 8 case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking turmeric and cancer medications that are CYP3A4 substrates, including everolimus, ruxolitinib, ibrutinib, and palbociclib, and bortezomib. In another case report, a transplant patient presented with acute nephrotoxicity and elevated tacrolimus levels after consuming turmeric powder at a dose of 15 or more spoonfuls daily for ten days prior. It was thought that turmeric increased levels of tacrolimus due to CYP3A4 inhibition.
Conversely, other in vitro research suggests that turmeric induces CYP3A4 activity, leading to reduced levels of CYP3A4 substrates. An animal model suggests that induction of CYP3A4 occurs after daily curcumin use for 1 week. However, the induction of CYP3A4 by turmeric has not been reported in humans.
Hepatotoxic Drugs
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
There is concern that turmeric might cause hepatotoxicity, especially when highly bioavailable formulations are used in high doses.
Methotrexate (Trexall, Others)
Theoretically, turmeric might have additive effects when used with hepatotoxic drugs such as methotrexate.
In one case report, a 39-year-old female taking methotrexate, turmeric, and linseed oil developed hepatotoxicity.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Theoretically, turmeric might increase blood levels of OATP4C1 substrates.
In vitro research shows that the turmeric constituent curcumin competitively inhibits OATP4C1 transport. This transporter is expressed in the kidney and facilitates the renal excretion of certain drugs. Theoretically, taking turmeric might decrease renal excretion of OATP substrates.
Sulfasalazine (Azulfidine)
Turmeric might increase the effects and adverse effects of sulfasalazine.
Clinical research shows that taking the turmeric constituent, curcumin, can increase blood levels of sulfasalazine by 3.2-fold.
Tacrolimus (Prograf)
Turmeric might increase the effects and adverse effects of tacrolimus.
In one case report, a transplant patient presented with acute nephrotoxicity and elevated tacrolimus levels of 29 ng/mL. The patient previously had tacrolimus levels within the therapeutic range at 9.7 ng/mL. Ten days prior to presenting at the emergency room the patient started consumption of turmeric powder at a dose of 15 or more spoonfuls daily. It was thought that turmeric increased levels of tacrolimus due to cytochrome P450 3A4 (CYP3A4) inhibition. In vitro and animal research show that turmeric and its constituent curcumin inhibit CYP3A4.
Talinolol
Turmeric may reduce the absorption of talinolol in some situations.
Clinical research shows that taking curcumin for 6 days decreases the bioavailability of talinolol when taken together on the seventh day. The clinical significance of this effect is unclear.
Tamoxifen (Nolvadex)
Theoretically, turmeric might reduce the levels and clinical effects of tamoxifen.
In a small clinical trial in patients with breast cancer taking tamoxifen 20-30 mg daily, adding curcumin 1200 mg plus piperine 10 mg three times daily reduces the 24-hour area under the curve of tamoxifen and the active metabolite endoxifen by 12.8% and 12.4%, respectively, as well as the maximum concentrations of tamoxifen, when compared with tamoxifen alone. However, in the absence of piperine, the area under the curve for endoxifen and the maximum concentration of tamoxifen were not significantly reduced. Effects were most pronounced in patients who were extensive cytochrome P450 (CYP) 2D6 metabolizers.
Topoisomerase I Inhibitors
Turmeric has antioxidant effects. There is some concern that this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro research shows that curcumin, a constituent of turmeric, inhibits camptothecin-induced apoptosis of breast cancer cells by up to 71%. However, other in vitro research shows that curcumin augments the cytotoxic effects of camptothecin. Reasons for the discrepancies may relate to the dose of curcumin and the chemotherapeutic agents. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effect, if any, turmeric might have.
Tramadol (Ultram)
Theoretically, turmeric might increase or decrease levels of tramadol.
Animal research suggests that a single dose of curcumin, a constituent of turmeric, may increase tramadol's maximum concentration (Cmax) by inhibiting metabolism, while continued daily use for 7 days may reduce the area under the curve (AUC) due to the induction of drug-metabolizing enzymes such as cytochrome P450 3A4 (CYP3A4). However, this interaction has not been reported in humans.
Warfarin (Coumadin)
Turmeric might increase the risk of bleeding with warfarin.
One case of increased international normalized ratio (INR) has been reported for a patient taking warfarin who began taking turmeric. Prior to taking turmeric, the patient had stable INR measurements. Within a few weeks of starting turmeric supplementation, the patient's INR increased to 10. Additionally, curcumin, the active constituent in turmeric, has demonstrated antiplatelet effects in vitro, which may produce additive effects when taken with warfarin.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2. However, research is conflicting.
In vitro and animal research show that the turmeric constituent, curcumin, inhibits CYP1A2. However, other in vitro research suggests that curcumin does not significantly affect CYP1A2.
Docetaxel (Taxotere)
Theoretically, turmeric might increase blood levels of oral docetaxel.
Animal research suggests that the turmeric constituent, curcumin, enhances the oral bioavailability of docetaxel. However, the significance of this interaction is unclear, as this drug is typically administered intravenously in clinical settings.
Estrogens
Theoretically, large amounts of turmeric might interfere with hormone replacement therapy through competition for estrogen receptors.
In vitro research shows that curcumin, a constituent of turmeric, displaces the binding of estrogen to its receptors.
Glyburide (Diabeta, Others)
Theoretically, taking turmeric and glyburide in combination might increase the risk of hypoglycemia.
Clinical research shows that taking curcumin 475 mg daily for 10 days prior to taking glyburide 5 mg increases blood levels of glyburide by 12% at 2 hours after the dose in patients with type 2 diabetes. While maximal blood concentrations of glyburide were not affected, turmeric modestly decreased postprandial glucose levels for up to 24 hours when compared to glyburide alone, possibly due to the hypoglycemic effect of turmeric demonstrated in animal research.
Losartan (Cozaar)
Theoretically, turmeric might increase the effects of losartan.
Research in hypertensive rats shows that taking turmeric can increase the hypotensive effects of losartan.
Norfloxacin (Noroxin)
Theoretically, turmeric might increase the effects and adverse effects of norfloxacin.
Animal research shows that taking curcumin, a turmeric constituent, can increase blood levels of orally administered norfloxacin.
P-Glycoprotein Substrates
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
In vitro and animal research shows that curcuminoids and other constituents found in turmeric can inhibit P-glycoprotein expression and activity.
Paclitaxel (Abraxane, Onxol)
Theoretically, turmeric might alter blood levels of paclitaxel, although any effect may not be clinically relevant.
Clinical research in adults with breast cancer receiving intravenous paclitaxel suggests that taking turmeric may modestly alter paclitaxel pharmacokinetics. Patients received paclitaxel on day 1, followed by either no treatment or turmeric 2 grams daily from days 2-22. Pharmacokinetic modeling suggests that turmeric reduces the maximum concentration and area under the curve of paclitaxel by 12.1% and 7.7%, respectively. However, these changes are not likely to be considered clinically relevant. Conversely, animal research suggests that curcumin, a constituent of turmeric, enhances the oral bioavailability of paclitaxel. However, the significance of this interaction is unclear, as this drug is typically administered intravenously in clinical settings.
Vitamin C
Alkylating Agents
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin C have on chemotherapy.
Aluminum
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Research in animals and humans shows that vitamin C increases aluminum absorption, theoretically by chelating aluminum and keeping it in solution where it is available for absorption. In people with normal renal function, urinary excretion of aluminum will likely increase, making aluminum retention and toxicity unlikely. Patients with renal failure who take aluminum-containing compounds such as phosphate binders should avoid vitamin C supplements in doses above the recommended dietary allowances.
Antitumor Antibiotics
Theoretically, the antioxidant effects of vitamin C might reduce the effectiveness of antitumor antibiotics.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as doxorubicin. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effects, if any, antioxidants such as vitamin C have on chemotherapy.
Estrogens
Vitamin C might increase blood levels of estrogens.
Increases in plasma estrogen levels of up to 55% occur under some circumstances when vitamin C is taken concurrently with oral contraceptives or hormone replacement therapy, including topical products. It is suggested that vitamin C prevents oxidation of estrogen in the tissues, regenerates oxidized estrogen, and reduces sulfate conjugation of estrogen in the gut wall. When tissue levels of vitamin C are high, these processes are already maximized and supplemental vitamin C does not have any effect on estrogen levels. Increases in plasma estrogen levels may occur when patients who are deficient in vitamin C take supplements. Monitor these patients for estrogen-related side effects.
Fluphenazine (Prolixin)
Theoretically, vitamin C might decrease levels of fluphenazine.
In one patient there was a clinically significant decrease in fluphenazine levels when vitamin C (500 mg twice daily) was started. The mechanism is not known, and there is no further data to confirm this interaction.
Indinavir (Crixivan)
Vitamin C can modestly reduce indinavir levels.
One pharmacokinetic study shows that taking vitamin C 1 gram orally once daily along with indinavir 800 mg orally three times daily reduces the area under the concentration-time curve of indinavir by 14%. The mechanism of this interaction is unknown, but it is unlikely to be clinically significant in most patients. The effect of higher doses of vitamin C on indinavir levels is unknown.
Levothyroxine (Synthroid, Others)
Vitamin C can increase levothyroxine absorption.
Two clinical studies in adults with poorly controlled hypothyroidism show that swallowing levothyroxine with a glass of water containing vitamin C 500-1000 mg in solution reduces thyroid stimulating hormone (TSH) levels and increases thyroxine (T4) levels when compared with taking levothyroxine alone. This suggests that vitamin C increases the oral absorption of levothyroxine, possibly due to a reduction in pH.
Warfarin (Coumadin)
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Vitamin C in high doses may cause diarrhea and possibly reduce warfarin absorption. There are reports of two people who took up to 16 grams daily of vitamin C and had a reduction in prothrombin time. Lower doses of 5-10 grams daily can also reduce warfarin absorption. In many cases, this does not seem to be clinically significant. However, a case of warfarin resistance has been reported for a patient who took vitamin C 500 mg twice daily. Cessation of vitamin C supplementation resulted in a rapid increase in international normalized ratio (INR). Tell patients taking warfarin to avoid taking vitamin C in excessively high doses (greater than 10 grams daily). Lower doses may be safe, but the anticoagulation activity of warfarin should be monitored. Patients who are stabilized on warfarin while taking vitamin C should avoid adjusting vitamin C dosage to prevent the possibility of warfarin resistance.
Acetaminophen (Tylenol, Others)
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
A small pharmacokinetic study in healthy volunteers shows that taking high-dose vitamin C (3 grams) 1.5 hours after taking acetaminophen 1 gram slightly increases the apparent half-life of acetaminophen from around 2.3 hours to 3.1 hours. Ascorbic acid competitively inhibits sulfate conjugation of acetaminophen. However, to compensate, elimination of acetaminophen glucuronide and unconjugated acetaminophen increases. This effect is not likely to be clinically significant.
Aspirin
Acidification of the urine by vitamin C might increase aspirin levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction is not clinically significant.
Choline Magnesium Trisalicylate (Trilisate)
Acidification of the urine by vitamin C might increase choline magnesium trisalicylate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Niacin
Vitamin C might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as vitamin C, or to the combination. It also is not known whether it will occur in other patient populations.
Salsalate (Disalcid)
Acidification of the urine by vitamin C might increase salsalate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams/day vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Inulin
Antidiabetes Drugs
Theoretically, inulin might increase the risk of hypoglycemia with antidiabetes drugs.
Some clinical research shows that inulin improves glycemic control in patients with diabetes; however, it is unclear if it has hypoglycemic effects.
Brand information
Manufacturer and brand details for Lactoferrin Gold 1.8, from the product label.
Nikken
See all Nikken products- Name
- Nikken Inc.
- Street Address
- 52 Discovery
- City
- Irvine
- State
- CA
- ZipCode
- 92618
- Web Address
- www.nikken.com
Lactoferrin Gold 1.8 by Nikken: Common Questions
Does Lactoferrin Gold 1.8 by Nikken interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take this if I'm on birth control?
What does lactoferrin do?
Will this cause stomach problems?
Is this safe during pregnancy?
Can I take this if I have diabetes?
Does this really help with anything?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Lactoferrin Gold 1.8 is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Lactoferrin Gold 1.8’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin C
Interacts with 207 drugsVitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for immune function, collagen, and acts as an...
Read the full Vitamin C monograph → Herb & supplement monographInulin
Interacts with 86 drugsInulin is a type of plant fiber (a prebiotic) found naturally in foods like chicory root, onions, and garlic, and it is widely added to supplements and processed foods. It may help with regu...
Read the full Inulin monograph → Herb & supplement monographTurmeric
Interacts with 1,133 drugsTurmeric is a popular spice whose main active compounds, curcuminoids, are studied mostly for inflammation and joint pain. Some research is promising, but quality is mixed and curcumin is po...
Read the full Turmeric monograph → Herb & supplement monographLactoferrin
Lactoferrin is an iron-binding protein found naturally in milk and other body fluids, and supplements are usually made from cow's milk or rice. It is being studied for immune support, iron l...
Read the full Lactoferrin monograph → Herb & supplement monographLecithin
Lecithin is a natural fatty substance found in foods and made by the body that is widely used as a supplement and food emulsifier. Evidence supporting most of its health claims is limited, t...
Read the full Lecithin monograph →Sources & How We Checked
Lactoferrin Gold 1.8's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 185 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Vitamin C 51 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Back DJ, Breckenridge AM, MacIver M, et al. Interaction of ethinyloestradiol with ascorbic acid in man. Br Med J (Clin Res Ed) 1981;282:1516.
- Morris JC, Beeley L, Ballantine N. Interaction of ethinyloestradiol with ascorbic acid in man [letter]. Br Med J (Clin Res Ed) 1981;283:503.
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Dwyer JH, Merz NB, Shirocre AM, et al. Progression of early atherosclerosis and intake of vitamin C and vitamin E from supplements and food. The Los Angeles Atherosclerosis Study. 41st Annual Conference on Cardiovascular Disease Epidemiology and Prevent
- Levine M, Rumsey SC, Daruwala R, et al. Criteria and recommendations for vitamin C intake. JAMA 1999;281:1415-23. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Houston JB, Levy G. Drug biotransformation interactions in man VI: Acetaminophen and ascorbic acid. J Pharm Sci 1976;65:1218-21. PubMed
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Rosenthal G. Interaction of ascorbic acid and warfarin. JAMA 1971;215:1671. DOI
- Hume R, Johnstone JM, Weyers E. Interaction of ascorbic acid and warfarin. JAMA 1972;219:1479. DOI
- Smith EC, Skalski RJ, Johnson GC, Rossi GV. Interaction of ascorbic acid and warfarin. JAMA 1972;221:1166. DOI
- Traxer O, Huet B, Poindexter J, et al. Effect of ascorbic acid consumption on urinary stone risk factors. J Urol 2003;170:397-401.. PubMed
- Domingo JL, Gomez M, Llobet JM, Richart C. Effect of ascorbic acid on gastrointestinal aluminum absorption (letter). Lancet 1991;338:1467.
- Domingo JL, Gomez M, Llobet JM, Corbella J. Influence of some dietary constituents on aluminum absorption and retention in rats. Kidney Int 1991;39:598-601. PubMed
- Partridge NA, Regnier FE, White JL, Hem SL. Influence of dietary constituents on intestinal absorption of aluminum. Kidney Int 1989;35:1413-7. PubMed
- Mc Leod DC, Nahata MC. Inefficacy of ascorbic acid as a urinary acidifier (letter). N Engl J Med 1977;296:1413. DOI
- Hansten PD, Hayton WL. Effect of antacid and ascorbic acid on serum salicylate concentration. J Clin Pharmacol 1980;20:326-31. PubMed
- Dysken MW, Cumming RJ, Channon RA, Davis JM. Drug interaction between ascorbic acid and fluphenazine. JAMA 1979;241:2008. DOI
- Vihtamaki T, Parantainen J, Koivisto AM, et al. Oral ascorbic acid increases plasma oestradiol during postmenopausal hormone replacement therapy. Maturitas 2002;42:129-35. PubMed
- Slain D, Amsden JR, Khakoo RA, et al. Effect of high-dose vitamin C on the steady-state pharmacokinetics of the protease inhibitor indinavir in healthy volunteers. Pharmacotherapy 2005;25:165-70. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Feetam CL, Leach RH, Meynell MJ. Lack of a clinically important interaction between warfarin and ascorbic acid. Toxicol Appl Pharmacol 1975;31:544-7. PubMed
- Weintraub M, Griner PF. Warfarin and ascorbic acid: lack of evidence for a drug interaction. Toxicol Appl Pharmacol 1974;28:53-6. PubMed
- Lee DH, Folsom AR, Harnack L, et al. Does supplemental vitamin C increase cardiovascular disease risk in women with diabetes? Am J Clin Nutr 2004;80:1194-200. PubMed
- Taylor EN, Stampfer MJ, Curhan GC. Dietary factors and the risk of incident kidney stones in men: new insights after 14 years of follow-up. J Am Soc Nephrol 2004;15:3225-32. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Fairweather-Tait S, Hickson K, McGaw B, et al. Orange juice enhances aluminium absorption from antacid preparation. Eur J Clin Nutr. 1994;48(1):71-3.
- Gruenwald, J., Graubaum, H. J., Busch, R., and Bentley, C. Safety and tolerance of ester-C compared with regular ascorbic acid. Adv.Ther. 2006;23(1):171-178.
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Einerson, B., Nathorn, C., Kitiyakara, C., Sirada, M., and Thamlikitkul, V. The efficacy of ascorbic acid in suboptimal responsive anemic hemodialysis patients receiving erythropoietin: a meta-analysis. J Med.Assoc.Thai. 2011;94 Suppl 1:S134-S146.
- Li, G., Li, L., Yu, C., and Chen, L. Effect of vitamins C and E supplementation on Helicobacter pylori eradication: a meta-analysis. Br.J Nutr 2011;106(11):1632-1637.
- Chen X, Shen L, Gu X, et al. High-dose supplementation with vitamin C--induced pediatric urolithiasis: the first case report in a child and literature review. Urology. 2014;84(4):922-4. PubMed
- Sattar A, Willman JE, Kolluri R. Possible warfarin resistance due to interaction with ascorbic acid: case report and literature review. Am J Health Syst Pharm. 2013;70(9):782-6. PubMed
- Yaich S, Chaabouni Y, Charfeddine K, et al. Secondary oxalosis due to excess vitamin C intake: a cause of graft loss in a renal transplant recipient. Saudi J Kidney Dis Transpl. 2014;25(1):113-6. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Rumbold A, Ota E, Nagata C, Shahrook S, Crowther CA. Vitamin C supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004072. PubMed
- Seo MS, Kim JK, Shim JY. High-dose vitamin C promotes regression of multiple pulmonary metastases originating from hepatocellular carcinoma. Yonsei Med J. 2015;56(5):1449-52. PubMed
- Skelin M, Lucijanic T, Amidzic Klaric D, et al. Factors Affecting Gastrointestinal Absorption of Levothyroxine: A Review. Clin Ther. 2017 Feb;39(2):378-403. PubMed
- Jiang K, Tang K, Liu H, Xu H, Ye Z, Chen Z. Ascorbic acid supplements and kidney stones incidence among men and women: a systematic review and meta-analysis. Urol J. 2019;16(2):115-120.
- Thomas S, Patel D, Bittel B, et al. Effect of High-Dose Zinc and Ascorbic Acid Supplementation vs Usual Care on Symptom Length and Reduction Among Ambulatory Patients With SARS-CoV-2 Infection: The COVID A to Z Randomized Clinical Trial. JAMA Netw Open. 2 PubMed
- Giffen MA, McLemore JL. Hyperoxalosis Secondary to Intravenous Vitamin C Administration as a Non-Allopathic Treatment for Cancer. Acad Forensic Pathol 2019;9(1-2):118-126. PubMed
- Maike A, Sturgill D, Gallan A. Oxalate Nephropathy in a Renal Transplant Recipient After Receiving High Dose Ascorbic Acid. Am J Med Sci 2021. PubMed
- Shen ZY, Chen YR, Wang MC, Chang SS. High-dose vitamin C-induced acute oxalate nephropathy in a renal transplant recipient: a case report and literature review. Asian J Surg 2022. PubMed
- Yanase F, Spano S, Maeda A, et al. Mega-dose sodium ascorbate: a pilot, single-dose, physiological effect, double-blind, randomized, controlled trial. Crit Care 2023;27(1):371. PubMed
- Sharma Y, Sumanadasa S, Shahi R, et al. Efficacy and safety of vitamin C supplementation in the treatment of community-acquired pneumonia: a systematic review and meta-analysis with trial sequential analysis. Sci Rep 2024;14(1):11846. PubMed
- Pejcic AV, Petrovic NZ, Djordjic MD, Milosavljevic MN. Vitamin C Levels in Pregnant Women and the Efficacy of Vitamin C Supplements in Preventing Premature Rupture of Membranes: A Systematic Review and Meta-Analysis. Balkan Med J 2024;41(4):248-260. PubMed
Inulin 17 references
- Williams CM. Effects of inulin on lipid parameters in humans. J Nutr 1999 Jul;129(7 Suppl):1471S-3S. PubMed
- Pedersen A, Sandstrom B, Van Amelsvoort JM. The effect of ingestion of inulin on blood lipids and gastrointestinal symptoms in healthy females. Br J Nutr 1997;78:215-22. PubMed
- Cummings JH, Macfarlane GT, Englyst HN. Prebiotic digestion and fermentation. Am J Clin Nutr 2001;73:415S-420S. PubMed
- Bonnema AL, Kolberg LW, Thomas W, Slavin JL. Gastrointestinal tolerance of chicory inulin products. J Am Diet Assoc 2010;110(6):865-8. PubMed
- Dehghan P, Gargari BP, Jafar-Abadi MA, Aliasgharzadeh A. Inulin controls inflammation and metabolic endotoxemia in women with type 2 diabetes mellitus: a randomized-controlled clinical trial. Int J Food Sci Nutr 2014;65(1):117-23. PubMed
- Guess ND, Dornhorst A, Oliver N, Frost GS. A randomised crossover trial: the effect of inulin on glucose homeostasis in subtypes of prediabetes. Ann Nutr Metab 2016;68(1):26-34. PubMed
- Marteau P, Jacobs H, Cazaubiel M, Signoret C, Prevel JM, Housez B. Effects of chicory inulin in constipated elderly people: a double-blind controlled trial. Int J Food Sci Nutr 2011;62(2):164-70. PubMed
- Mensink MA, Frijlink HW, van der Voort Maarschalk K, Hinrichs WL. Inulin, a flexible oligosaccharide I: review of its physicochemical characteristics. Carbohydr Polym 2015;130:405-19. PubMed
- Slavin J, Feirtag J. Chicory inulin does not increase stool weight or speed up intestinal transit time in healthy male subjects. Food Funct. 2011;2(1):72-7. PubMed
- Micka A, Siepelmeyer A, Holz A, Theis S, Schön C. Effect of consumption of chicory inulin on bowel function in healthy subjects with constipation: a randomized, double-blind, placebo-controlled trial. Int J Food Sci Nutr. 2017;68(1):82-89. PubMed
- Smiljanec K, Mitchell CM, Privitera OF, Neilson AP, Davy KP, Davy BM. Pre-meal inulin consumption does not affect acute energy intake in overweight and obese middle-aged and older adults: A randomized controlled crossover pilot trial. Nutr Health. 2017;23 PubMed
- Cai X, Yu H, Liu L, et al. Milk powder co-supplemented with inulin and resistant dextrin improves glycemic control and insulin resistance in elderly type 2 diabetes mellitus: a 12-week randomized, double-blind, placebo-controlled trial. Mol Nutr Food Res PubMed
- Rao M, Gao C, Xu L, et al. Effect of inulin-type carbohydrates on insulin resistance in patients with type 2 diabetes and obesity: a systematic review and meta-analysis. J Diabetes Res. 2019;2019:5101423. PubMed
- Mitchell CM, Davy BM, Ponder MA, et al. Prebiotic Inulin Supplementation and Peripheral Insulin Sensitivity in adults at Elevated Risk for Type 2 Diabetes: A Pilot Randomized Controlled Trial. Nutrients 2021;13(9):3235. PubMed
- Li L, Li P, Xu L. Assessing the effects of inulin-type fructan intake on body weight, blood glucose, and lipid profile: A systematic review and meta-analysis of randomized controlled trials. Food Sci Nutr 2021;9(8):4598-4616. PubMed
- Ziaei R, Shahshahan Z, Ghasemi-Tehrani H, Heidari Z, Ghiasvand R. Effects of inulin-type fructans with different degrees of polymerization on inflammation, oxidative stress and endothelial dysfunction in women with polycystic ovary syndrome: A randomized,
- Risso D, Kaczmarczyk M, Laurie I, et al. Moderate intakes of soluble corn fibre or inulin do not cause gastrointestinal discomfort and are well tolerated in healthy children. Int J Food Sci Nutr 2022;73(8):1104-1115. PubMed
Turmeric 102 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Sharma RA, McLelland HR, Hill KA, et al. Pharmacodynamic and pharmacokinetic study of oral Curcuma extract in patients with colorectal cancer. Clin Cancer Res 2001;7:1894-900..
- Shah BH, Nawaz Z, Pertani SA. Inhibitory effect of curcumin, a food spice from turmeric, on platelet-activating factor- and arachidonic acid-mediated platelet aggregation through inhibition of thromboxane formation and Ca2+ signaling. Biochem Pharmacol 1 PubMed
- Hata M, Sasaki E, Ota M, et al . Allergic contact dermatitis from curcumin (turmeric). Contact Dermatitis 1997;36:107-8. PubMed
- Kuttan R, Sudheeran PC, Josph CD. Turmeric and curcumin as topical agents in cancer therapy. Tumori 1987;73:29-31.. PubMed
- Thapliyal R, Deshpande SS, Maru GB. Mechanism(s) of turmeric-mediated protective effects against benzo(a)pyrene-derived DNA adducts. Cancer Lett 2002;175:79-88. PubMed
- Lee SW, Nah SS, Byon JS, et al. Transient complete atrioventricular block associated with curcumin intake. Int J Cardiol 2011;150:e50-2. PubMed
- Kuptniratsaikul V, Thanakhumtorn S, Chinswangwatanakul P, et al. Efficacy and safety of Curcuma domestica extracts in patients with knee osteoarthritis. J Altern Complement Med 2009;15:891-7.
- Carroll RE, Benya RV, Turgeon DK, et al. Phase IIa clinical trial of curcumin for the prevention of colorectal neoplasia. Cancer Prev Res (Phila) 2011;4:354-64. PubMed
- Junyaprasert, V. B., Soonthornchareonnon, N., Thongpraditchote, S., Murakami, T., and Takano, M. Inhibitory effect of Thai plant extracts on P-glycoprotein mediated efflux. Phytother.Res 2006;20(1):79-81. PubMed
- Ampasavate, C., Sotanaphun, U., Phattanawasin, P., and Piyapolrungroj, N. Effects of Curcuma spp. on P-glycoprotein function. Phytomedicine. 2010;17(7):506-512. PubMed
- Hou, X. L., Takahashi, K., Tanaka, K., Tougou, K., Qiu, F., Komatsu, K., Takahashi, K., and Azuma, J. Curcuma drugs and curcumin regulate the expression and function of P-gp in Caco-2 cells in completely opposite ways. Int.J Pharm 6-24-2008;358(1-2):224-2 PubMed
- Choi, B. H., Kim, C. G., Lim, Y., Shin, S. Y., and Lee, Y. H. Curcumin down-regulates the multidrug-resistance mdr1b gene by inhibiting the PI3K/Akt/NF kappa B pathway. Cancer Lett. 1-18-2008;259(1):111-118.
- Zhang, W., Tan, T. M., and Lim, L. Y. Impact of curcumin-induced changes in P-glycoprotein and CYP3A expression on the pharmacokinetics of peroral celiprolol and midazolam in rats. Drug Metab Dispos. 2007;35(1):110-115. PubMed
- Limtrakul, P., Chearwae, W., Shukla, S., Phisalphong, C., and Ambudkar, S. V. Modulation of function of three ABC drug transporters, P-glycoprotein (ABCB1), mitoxantrone resistance protein (ABCG2) and multidrug resistance protein 1 (ABCC1) by tetrahydrocu
- Holland, M. L., Panetta, J. A., Hoskins, J. M., Bebawy, M., Roufogalis, B. D., Allen, J. D., and Arnold, J. C. The effects of cannabinoids on P-glycoprotein transport and expression in multidrug resistant cells. Biochem.Pharmacol 4-14-2006;71(8):1146-1154 PubMed
- Tang, X. Q., Bi, H., Feng, J. Q., and Cao, J. G. Effect of curcumin on multidrug resistance in resistant human gastric carcinoma cell line SGC7901/VCR. Acta Pharmacol Sin. 2005;26(8):1009-1016. PubMed
- Nabekura, T., Kamiyama, S., and Kitagawa, S. Effects of dietary chemopreventive phytochemicals on P-glycoprotein function. Biochem.Biophys.Res Commun. 2-18-2005;327(3):866-870. PubMed
- Romiti, N., Tongiani, R., Cervelli, F., and Chieli, E. Effects of curcumin on P-glycoprotein in primary cultures of rat hepatocytes. Life Sci. 1998;62(25):2349-2358. PubMed
- Yue, G. G., Cheng, S. W., Yu, H., Xu, Z. S., Lee, J. K., Hon, P. M., Lee, M. Y., Kennelly, E. J., Deng, G., Yeung, S. K., Cassileth, B. R., Fung, K. P., Leung, P. C., and Lau, C. B. The role of turmerones on curcumin transportation and P-glycoprotein acti
- Shenouda, N. S., Zhou, C., Browning, J. D., Ansell, P. J., Sakla, M. S., Lubahn, D. B., and MacDonald, R. S. Phytoestrogens in common herbs regulate prostate cancer cell growth in vitro. Nutr.Cancer 2004;49(2):200-208. PubMed
- Appiah-Opong, R., Commandeur, J. N., Vugt-Lussenburg, B., and Vermeulen, N. P. Inhibition of human recombinant cytochrome P450s by curcumin and curcumin decomposition products. Toxicology 6-3-2007;235(1-2):83-91. PubMed
- Hou, X. L., Takahashi, K., Kinoshita, N., Qiu, F., Tanaka, K., Komatsu, K., Takahashi, K., and Azuma, J. Possible inhibitory mechanism of Curcuma drugs on CYP3A4 in 1alpha,25 dihydroxyvitamin D3 treated Caco-2 cells. Int.J Pharm 6-7-2007;337(1-2):169-177.
- Valentine, S. P., Le Nedelec, M. J., Menzies, A. R., Scandlyn, M. J., Goodin, M. G., and Rosengren, R. J. Curcumin modulates drug metabolizing enzymes in the female Swiss Webster mouse. Life Sci. 4-11-2006;78(20):2391-2398. PubMed
- Price, R. J., Scott, M. P., Giddings, A. M., Walters, D. G., Stierum, R. H., Meredith, C., and Lake, B. G. Effect of butylated hydroxytoluene, curcumin, propyl gallate and thiabendazole on cytochrome P450 forms in cultured human hepatocytes. Xenobiotica 2 PubMed
- Ganta, S., Devalapally, H., and Amiji, M. Curcumin enhances oral bioavailability and anti-tumor therapeutic efficacy of paclitaxel upon administration in nanoemulsion formulation. J Pharm Sci 2010;99(11):4630-4641. PubMed
- Lamb, S. R. and Wilkinson, S. M. Contact allergy to tetrahydrocurcumin. Contact Dermatitis 2003;48(4):227. PubMed
- Joshi, J., Ghaisas, S., Vaidya, A., Vaidya, R., Kamat, D. V., Bhagwat, A. N., and Bhide, S. Early human safety study of turmeric oil (Curcuma longa oil) administered orally in healthy volunteers. J Assoc.Physicians India 2003;51:1055-1060.
- Mahesh, T., Balasubashini, M. S., and Menon, V. P. Effect of photo-irradiated curcumin treatment against oxidative stress in streptozotocin-induced diabetic rats. J Med.Food 2005;8(2):251-255. PubMed
- Thompson, D. A. and Tan, B. B. Tetrahydracurcumin-related allergic contact dermatitis. Contact Dermatitis 2006;55(4):254-255. PubMed
- Patumraj, S., Wongeakin, N., Sridulyakul, P., Jariyapongskul, A., Futrakul, N., and Bunnag, S. Combined effects of curcumin and vitamin C to protect endothelial dysfunction in the iris tissue of STZ-induced diabetic rats. Clin Hemorheol.Microcirc. 2006;3
- Liddle, M., Hull, C., Liu, C., and Powell, D. Contact urticaria from curcumin. Dermatitis 2006;17(4):196-197. PubMed
- Juan, H., Terhaag, B., Cong, Z., Bi-Kui, Z., Rong-Hua, Z., Feng, W., Fen-Li, S., Juan, S., Jing, T., and Wen-Xing, P. Unexpected effect of concomitantly administered curcumin on the pharmacokinetics of talinolol in healthy Chinese volunteers. Eur.J Clin PubMed
- Murugan, P. and Pari, L. Influence of tetrahydrocurcumin on erythrocyte membrane bound enzymes and antioxidant status in experimental type 2 diabetic rats. J Ethnopharmacol. 9-25-2007;113(3):479-486. PubMed
- Seo, K. I., Choi, M. S., Jung, U. J., Kim, H. J., Yeo, J., Jeon, S. M., and Lee, M. K. Effect of curcumin supplementation on blood glucose, plasma insulin, and glucose homeostasis related enzyme activities in diabetic db/db mice. Mol.Nutr.Food Res 2008;5
- Weisberg, S. P., Leibel, R., and Tortoriello, D. V. Dietary curcumin significantly improves obesity-associated inflammation and diabetes in mouse models of diabesity. Endocrinology 2008;149(7):3549-3558. PubMed
- Jain, S. K., Rains, J., Croad, J., Larson, B., and Jones, K. Curcumin supplementation lowers TNF-alpha, IL-6, IL-8, and MCP-1 secretion in high glucose-treated cultured monocytes and blood levels of TNF-alpha, IL-6, MCP-1, glucose, and glycosylated hemog
- Yu, Y., Hu, S. K., and Yan, H. [The study of insulin resistance and leptin resistance on the model of simplicity obesity rats by curcumin]. Zhonghua Yu Fang Yi.Xue.Za Zhi. 2008;42(11):818-822.
- Pavithra, B. H., Prakash, N., and Jayakumar, K. Modification of pharmacokinetics of norfloxacin following oral administration of curcumin in rabbits. J Vet.Sci. 2009;10(4):293-297. PubMed
- Yan, Y. D., Kim, D. H., Sung, J. H., Yong, C. S., and Choi, H. G. Enhanced oral bioavailability of docetaxel in rats by four consecutive days of pre-treatment with curcumin. Int J Pharm 10-31-2010;399(1-2):116-120. PubMed
- Epelbaum, R., Schaffer, M., Vizel, B., Badmaev, V., and Bar-Sela, G. Curcumin and gemcitabine in patients with advanced pancreatic cancer. Nutr Cancer 2010;62(8):1137-1141. PubMed
- Madkor, H. R., Mansour, S. W., and Ramadan, G. Modulatory effects of garlic, ginger, turmeric and their mixture on hyperglycaemia, dyslipidaemia and oxidative stress in streptozotocin-nicotinamide diabetic rats. Br J Nutr 2011;105(8):1210-1217. PubMed
- Pungcharoenkul, K. and Thongnopnua, P. Effect of different curcuminoid supplement dosages on total in vivo antioxidant capacity and cholesterol levels of healthy human subjects. Phytother Res 2011;25(11):1721-1726.
- Kusuhara, H., Furuie, H., Inano, A., Sunagawa, A., Yamada, S., Wu, C., Fukizawa, S., Morimoto, N., Ieiri, I., Morishita, M., Sumita, K., Mayahara, H., Fujita, T., Maeda, K., and Sugiyama, Y. Pharmacokinetic interaction study of sulphasalazine in healthy
- Mohammadi, A., Sahebkar, A., Iranshahi, M., Amini, M., Khojasteh, R., Ghayour-Mobarhan, M., and Ferns, G. A. Effects of supplementation with curcuminoids on dyslipidemia in obese patients: a randomized crossover trial. Phytother Res 2013;27(3):374-379. PubMed
- Chuengsamarn, S., Rattanamongkolgul, S., Luechapudiporn, R., Phisalaphong, C., and Jirawatnotai, S. Curcumin extract for prevention of type 2 diabetes. Diabetes Care 2012;35(11):2121-2127. PubMed
- Goh, C. L. and Ng, S. K. Allergic contact dermatitis to Curcuma longa (turmeric). Contact Dermatitis 1987;17(3):186. PubMed
- Srivastava, R., Puri, V., Srimal, R. C., and Dhawan, B. N. Effect of curcumin on platelet aggregation and vascular prostacyclin synthesis. Arzneimittelforschung. 1986;36(4):715-717.
- Srinivasan, M. Effect of curcumin on blood sugar as seen in a diabetic subject. Indian J Med Sci 1972;26(4):269-270.
- Srivastava, K. C., Bordia, A., and Verma, S. K. Curcumin, a major component of food spice turmeric (Curcuma longa) inhibits aggregation and alters eicosanoid metabolism in human blood platelets. Prostaglandins Leukot.Essent.Fatty Acids 1995;52(4):223-227 PubMed
- Oetari, S., Sudibyo, M., Commandeur, J. N., Samhoedi, R., and Vermeulen, N. P. Effects of curcumin on cytochrome P450 and glutathione S-transferase activities in rat liver. Biochem Pharmacol 1-12-1996;51(1):39-45. PubMed
- Kiec-Swierczynska, M. and Krecisz, B. Occupational allergic contact dermatitis due to curcumin food colour in a pasta factory worker. Contact Dermatitis 1998;39(1):30-31. PubMed
- Van Dau N, Ngoc Ham N, Huy Khac D, and et al. The effects of a traditional drug, tumeric (Curcuma longa), and placebo on the healing of duodenal ulcer. Phytomed 1998;5(1):29-34.
- Daveluy A, Géniaux H, Thibaud L, Mallaret M, Miremont-Salamé G, Haramburu F. Probable interaction between an oral vitamin K antagonist and turmeric (Curcuma longa). Therapie. 2014 Nov-Dec;69(6):519-20. PubMed
- Kuptniratsaikul V, Dajpratham P, Taechaarpornkul W, Buntragulpoontawee M, Lukkanapichonchut P, Chootip C, Saengsuwan J, Tantayakom K, Laongpech S. Efficacy and safety of Curcuma domestica extracts compared with ibuprofen in patients with knee osteoarthrit
- Madhu K, Chanda K, Saji MJ. Safety and efficacy of Curcuma longa extract in the treatment of painful knee osteoarthritis: a randomized placebo-controlled trial. Inflammopharmacology 2013;21(2):129-36. PubMed
- Mali AM, Behal R, Gilda SS. Comparative evaluation of 0.1% turmeric mouthwash with 0.2% chlorhexidine gluconate in prevention of plaque and gingivitis: A clinical and microbiological study. J Indian Soc Periodontol 2012;16(3):386-91. PubMed
- Sanmukhani J, Satodia V, Trivedi J, Patel T, Tiwari D, Panchal B, Goel A, Tripathi CB. Efficacy and safety of curcumin in major depressive disorder: a randomized controlled trial. Phytother Res 2014;28(4):579-85. PubMed
- Nayeri A, Wu S, Adams E, et al. Acute Calcineurin Inhibitor Nephrotoxicity Secondary to Turmeric Intake: A Case Report. Transplant Proc. 2017;49(1):198-200. PubMed
- Mitchell TM. Correspondence re: Somasundaram et al., Dietary curcumin inhibits chemotherapy-induced apoptosis in models of human breast cancer. Cancer Res. 2003;63(16):5165-6; author reply 5166-7.
- Somasundaram S, Edmund NA, Moore DT, Small GW, Shi YY, Orlowski RZ. Dietary curcumin inhibits chemotherapy-induced apoptosis in models of human breast cancer. Cancer Res. 2002;62(13):3868-75.
- Haroyan A, Mukuchyan V, Mkrtchyan N, et al. Efficacy and safety of curcumin and its combination with boswellic acid in osteoarthritis: a comparative, randomized, double-blind, placebo-controlled study. BMC Complement Altern Med. 2018;18(1):7. PubMed
- Al-Karawi D, Al Mamoori DA, Tayyar Y. The role of curcumin administration in patients with major depressive disorder: Mini meta-analysis of clinical trials. Phytother Res. 2016;30(2):175-83. PubMed
- Neerati P, Devde R, Gangi AK. Evaluation of the effect of curcumin capsules on glyburide therapy in patients with type-2 diabetes mellitus. Phytother Res. 2014;28(12):1796-800. PubMed
- Simental-Mendía LE, Pirro M, Gotto AM Jr, et al. Lipid-modifying activity of curcuminoids: A systematic review and meta-analysis of randomized controlled trials. Crit Rev Food Sci Nutr. 2017:1-10. PubMed
- Fung FY, Wong WH, Ang SK, et al. A randomized, double-blind, placebo- controlled study on the anti-haemostatic effects of Curcuma longa, Angelica sinensis and Panax ginseng. Phytomedicine. 2017;32:88-96. PubMed
- Small GW, Siddarth P, Li Z, et al. Memory and brain amyloid and tau effects of a bioavailable form of curcumin in non-demented adults: A double-blind, placebo-controlled 18-month trial. Am J Geriatr Psychiatry. 2018;26(3):266-277.
- Cruz-Correa M, Hylind LM, Marrero JH, et al. Efficacy and safety of curcumin in treatment of intestinal adenomas in patients with familial adenomatous polyposis. Gastroenterology. 2018 May 23. Pii:S0016-5085(18)34564-5. [Epub ahead of print] PubMed
- Rahmani S, Asgary S, Askari G, et al. Treatment of non-alcoholic fatty liver disease with curcumin: a randomized placebo-controlled trial. Phytother Res. 2016 Sep;30(9):1540-8. PubMed
- Lopez-Villafuerte L, CLores KH. Contact dermatitis caused by turmeric in a massage oil. Contact Dermatitis. 2016 Jul;75(1):52-3. PubMed
- Lukefahr AL, McEvoy S, Alfafara C, Funk JL. Drug-induced autoimmune hepatitis associated with turmeric dietary supplement use. BMJ Case Rep. 2018. pii: bcr-2018-224611. PubMed
- Medsafe Safety Communication- Turmeric/Curcumin Interaction with Warfarin. April 30, 2018. Accessed at: https://medsafe.govt.nz/safety/EWS/2018/Turmeric.asp.
- Imam Z, Khasawneh M, Jomaa D, Iftikhar H, Sayedahmad Z. Drug induced liver injury attributed to a curcumin supplement. Case Rep Gastrointest Med 2019 Oct 20;2019:6029403. doi: 10.1155/2019/6029403. PubMed
- Chand S, Hair C, Beswick L. A rare case of turmeric-induced hepatotoxicity. Intern Med J. 2020;50(2):258-259. PubMed
- Jiang N, Zhang M, Meng X, Sun B. Effects of Curcumin on the Pharmacokinetics of Amlodipine in Rats and Its Potential Mechanism. Pharm Biol. 2020;58(1):465-468. PubMed
- Lee BS, Bhatia T, Chaya CT, Wen R, Taira MT, Lim BS. Autoimmune Hepatitis Associated With Turmeric Consumption. ACG Case Rep J. 2020;7(3):e00320. PubMed
- Lombardi N, Crescioli G, Maggini V, et al. Acute liver injury following turmeric use in Tuscany: an analysis of the Italian Phytovigilance database and systematic review of case reports. Br J Clin Pharmacol. 2020. PubMed
- Suhail FK, Masood U, Sharma A, John S, Dhamoon A. Turmeric supplement induced hepatotoxicity: a rare complication of a poorly regulated substance. Clin Toxicol (Phila). 2020;58(3):216-217. PubMed
- Nakagawa Y, Mukai S, Yamada S, et al. The efficacy and safety of highly-bioavailable curcumin for treating knee osteoarthritis: a 6-month open-labeled prospective study. Clin Med Insights Arthritis Musculoskelet Disord. 2020;13:1179544120948471. PubMed
- Shafabakhsh R, Asemi Z, Reiner Z, Soleimani A, Aghadavod E, Bahmani F. The effects of nano-curcumin on metabolic status in patients with diabetes on hemodialysis, a randomized, double blind, placebo-controlled trial. Iran J Kidney Dis. 2020;14(4):290-9.
- Allegri P, Rosa R, Masala A, et al. Clinical effectiveness of a new oral curcumin formulation in acute non-infectious uveitic macular edema: a 12-month observational study. Eur Rev Med Pharmacol Sci 2022;26(1):46-53.
- Tsai IC, Hsu CW, Chang CH, Tseng PT, Chang KV. The effect of curcumin differs on individual cognitive domains across different patient populations: A systematic review and meta-analysis. Pharmaceuticals (Basel) 2021;14(12):1235. PubMed
- Alam MA, Bin Jardan YA, Raish M, Al-Mohizea AM, Ahad A, Al-Jenoobi FI. Herb-drug interaction: Pharmacokinetics and pharmacodynamics of anti-hypertensive drug amlodipine besylate in presence of lepidium sativum and curcuma longa. Xenobiotica 2022;1-9.
- Sohal A, Alhankawi D, Sandhu S, Chintanaboina J. Turmeric-induced hepatotoxicity: Report of 2 cases. Int Med Case Rep J 2021;14:849-852. PubMed
- Hussaarts KGAM, Hurkmans DP, Oomen-de Hoop E, et al. Impact of curcumin (with or without piperine) on the pharmacokinetics of tamoxifen. Cancers (Basel). 2019;11(3):403. PubMed
- Kalluru H, Mallayasamy SR, Kondaveeti SS, Chandrasekhar V, Kalachaveedu M. Effect of turmeric supplementation on the pharmacokinetics of paclitaxel in breast cancer patients: A study with population pharmacokinetics approach. Phytother Res 2022;36(4):1761 PubMed
- 109288 Halegoua-DeMarzio D, Navarro V, Ahmad J, et al. Liver injury associated with turmeric-A growing problem: Ten cases from the drug-induced liver injury network [DILIN]. Am J Med. 2022:S0002-9343(22)00740-9. PubMed
- Arzallus T, Izagirre A, Castiella A, Torrente S, Garmendia M, Zapata EM. Drug induced autoimmune hepatitis after turmeric intake. Gastroenterol Hepatol 2023. PubMed
- Gilad O, Rosner G, Ivancovsky-Wajcman D, et al. Efficacy of wholistic turmeric supplement on adenomatous polyps in patients with familial adenomatous polyposis-A randomized, double-blinded, placebo-controlled study. Genes (Basel) 2022;13(12):2182. PubMed
- Ahad A, Raish M, Abdelrahman IA, et al. Changes in pharmacokinetics and pharmacodynamics of losartan in experimental diseased rats treated with Curcuma longa and Lepidium sativum. Pharmaceuticals (Basel) 2022;16(1):33. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
- Kou H, Huang L, Jin M, He Q, Zhang R, Ma J. Effect of curcumin on rheumatoid arthritis: a systematic review and meta-analysis. Front Immunol 2023;14:1121655. PubMed
- Qiu L, Gao C, Wang H, et al. Effects of dietary polyphenol curcumin supplementation on metabolic, inflammatory, and oxidative stress indices in patients with metabolic syndrome: a systematic review and meta-analysis of randomized controlled trials. Front PubMed
- Sato T, Yagi A, Yamauchi M, et al. The use of an antioxidant enables accurate evaluation of the interaction of curcumin on organic anion-transporting polypeptides 4C1 by preventing auto-oxidation. Int J Mol Sci 2024;25(2):991. PubMed
- Washington O, Robinson E, Simh D, et al. Oxalate nephropathy and chronic turmeric supplementation: a case report. J Bras Nefrol 2024;46(1):99-106. PubMed
- Munshi R, Karande-Patil S, Kumbhar D, Deshmukh A, Hingorani L. A randomized, controlled, comparative, proof-of-concept study to evaluate the efficacy and safety of Nisha-Amalaki capsules in prediabetic patients for preventing progression to diabetes. J Ay PubMed
- Sharifi Razavi A, Mohajerani F, Niksolat F, Karimi N. Efficacy of topical curcumin on mild to moderate carpal tunnel syndrome: a randomized double-blind, placebo-controlled clinical trial. Pain Med 2024;25(5):327-333. PubMed
- Yaikwawong M, Jansarikit L, Jirawatnotai S, Chuengsamarn S. Curcumin Reduces Depression in Obese Patients with Type 2 Diabetes: A Randomized Controlled Trial. Nutrients 2024;16(15):2414. PubMed
- Tehrani SD, Hosseini A, Shahzamani M, et al. Evaluation of the effectiveness of curcumin and piperine co-supplementation on inflammatory factors, cardiac biomarkers, atrial fibrillation, and clinical outcomes after coronary artery bypass graft surgery. Cl PubMed
- Yaikwawong M, Jansarikit L, Jirawatnotai S, Chuengsamarn S. The Effect of Curcumin on Reducing Atherogenic Risks in Obese Patients with Type 2 Diabetes: A Randomized Controlled Trial. Nutrients 2024;16(15):2441. PubMed
- Dibaei M, Hosseini A, Lavasani H, Kiani-Dehkordi B, Rouini M. Assessment of metabolic interaction between curcumin and tramadol using the isolated perfused rat liver. Heliyon 2024;10(15):e35070. PubMed
Lactoferrin 6 references
- Food and Drug Administration, CFSAN/Office of Food Additive Safety. Agency Response Letter GRAS Notice No. GRN 000130. 2003. Available at: http://www.cfsan.fda.gov/~rdb/opa-g130.html (Accessed 29 June 2005).
- Okada S, Tanaka K, Sato T, et al. Dose-response trial of lactoferrin in patients with chronic hepatitis C. Jpn J Cancer Res 2002;93:1063-9. PubMed
- Abu Hashim H, Foda O, Ghayaty E. Lactoferrin or ferrous salts for iron deficiency anemia in pregnancy: A meta-analysis of randomized trials. Eur J Obstet Gynecol Reprod Biol. 2017;219:45-52. PubMed
- Tarnow-Mordi WO, Abdel-Latif ME, Martin A, et al. The effect of lactoferrin supplementation on death or major morbidity in very low birthweight infants (LIFT): a multicentre, double-blind, randomised controlled trial. Lancet Child Adolesc Health. 2020 Jun PubMed
- ELFIN trial investigators group. Enteral lactoferrin supplementation for very preterm infants: a randomised placebo-controlled trial. Lancet. 2019 Feb 2;393(10170):423-433. doi: 10.1016/S0140-6736(18)32221-9.
- Lepanto MS, Rosa L, Cutone A, Conte MP, Paesano R, Valenti P. Efficacy of lactoferrin oral administration in the treatment of anemia and anemia of inflammation in pregnant and non-pregnant women: An interventional study. Front Immunol. 2018 Sep 21;9:2123. PubMed
Lecithin 9 references
- Buchman AL, Dubin M, Jenden D, et al. Lecithin increases plasma free choline and decreases hepatic steatosis in long-term total parenteral nutrition patients. Gastroenterology 1992;102:1363-70.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Chatellier G, Lacomblez L. Tacrine (tetrahydroaminoacridine; THA) and lecithin in senile dementia of the Alzheimer type: a multicentre trial. Groupe Francais d'Etude de la Tetrahydroaminoacridine. BMJ 1990;300:495-9.
- Gelenberg AJ, Dorer DJ, Wojcik JD, et al. A crossover study of lecithin treatment of tardive dyskinesia. J Clin Psychiatry 1990;51:149-53.
- Little A, Levy R, Chuaqui-Kidd P, Hand D. A double-blind, placebo controlled trial of high-dose lecithin in Alzheimer's disease. J Neurol Neurosurg Psychiatry 1985;48:736-42. PubMed
- Palm M, Moneret-Vautrin DA, Kanny G, et al. Food allergy to egg and soy lecithins. Allergy 1999;54:1116-7. PubMed
- Drachman DA, Glosser G, Fleming P, et al. Memory decline in the aged: treatment with lecithin and physostigmine. Neurology 1982;32:944-50. PubMed
- Gelenberg, A. J., Doller-Wojcik, J. C., and Growdon, J. H. Choline and lecithin in the treatment of tardive dyskinesia: preliminary results from a pilot study. Am J Psychiatry 1979;136(6):772-776. PubMed
- Electronic Code of Federal Regulations. Title 21, Chapter 1, Subchapter B, Part 184: Direct food substances affirmed as Generally Recognized as Safe. Subpart B - listing of specific substances affirmed as GRAS. Sec. 184.1400 Lecithin. Available at: https:
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC