
Lipo Plus Ingredients & Drug Interactions
by Priority One Nutritional Supplements
What is this page for?
First and foremost: checking Lipo Plus against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Lipo Plus is a dietary supplement by Priority One Nutritional Supplements with 16 active ingredients. Its ingredients are commonly taken for morning sickness in pregnancy, premenstrual syndrome (pms), preventing or treating b6 deficiency.Based on those ingredients, 1,700 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Green Tea, Barberry, Milk Thistle Seed Extract. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Lipo Plus by Priority One Nutritional Supplements
Ask about any prescription or over-the-counter medication and we check it for interactions with Lipo Plus by Priority One Nutritional Supplements — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Lipo Plus by Priority One Nutritional Supplements
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
Lipo Plus contains 16 ingredients, of which the active ones include vitamin B6, choline bitartrate, inositol, magnesium, milk thistle seed extract, dandelion root extract, black radish, barberry, beet, greater celandine, and green tea. The remaining ingredients are tissue concentrates (pituitary, duodenum, pancreatin) and ox bile, plus DL-methionine, an amino acid derivative.
The inactive ingredients are standard tablet fillers and binders: dicalcium phosphate, stearic acid, microcrystalline cellulose, silicon dioxide, croscarmellose sodium, magnesium stearate, and methyl cellulose.
Does it work?
Strong evidence
The evidence for Lipo Plus's ingredients varies widely. Vitamin B6 is effective for sideroblastic anemia and B6 deficiency, and likely effective for lowering homocysteine; it's possibly effective for pregnancy-induced nausea.
Inositol is possibly effective for polycystic ovary syndrome and metabolic syndrome. Magnesium is effective for constipation and dyspepsia, and effective for preventing pre-eclampsia in pregnancy.
Milk thistle is possibly effective for diabetes. Beet is possibly effective for athletic performance and exercise-induced muscle soreness.
For most of the other ingredients—choline, dandelion, black radish, barberry, celandine, and green tea—we either lack sufficient evidence or the data shows they are possibly ineffective for their proposed uses. No evidence in our data supports this product's overall purpose.
How safe is it?
Well-documented data
Vitamin B6 is generally well tolerated at doses under 100 mg daily, though high doses over time can cause nerve damage (sensory neuropathy). Choline is generally safe in food amounts but can cause fishy body odor, and at doses above 3.5 grams daily may cause gastrointestinal upset.
Inositol is well tolerated with mostly mild digestive side effects (diarrhea, gas, nausea). Magnesium is generally well tolerated but commonly causes diarrhea, nausea, and gastrointestinal irritation at higher doses.
Milk thistle, dandelion, black radish, and beet are generally well tolerated as foods; concentrated supplements have less safety data. Greater celandine has been linked to dozens of cases of liver damage and is concerning for long-term use.
Green tea is generally safe as a beverage but high-dose extracts have rarely caused liver injury. For pregnancy: vitamin B6 is likely safe, inositol is possibly safe, and magnesium is likely to possibly safe; however, barberry and greater celandine should be avoided, milk thistle should be avoided, and dandelion has insufficient data.
For breastfeeding: vitamin B6 and choline are likely safe; barberry and greater celandine should be avoided; and most others have limited or no safety data.
Meds to double-check
Major interaction found
Before taking Lipo Plus, double-check with your pharmacist or doctor if you use any of these: levodopa/carbidopa (Sinemet)—magnesium can cut drug levels sharply; nadolol (Corgard), atorvastatin (Lipitor), or ephedrine—green tea can reduce or interfere with these drugs' effects. Also discuss it if you take antihypertensive drugs, seizure medications (phenobarbital, phenytoin, felbamate, valproate, ethosuximide), antidiabetes drugs, anticoagulants or antiplatelets, skeletal muscle relaxants, potassium-sparing diuretics, quinolone antibiotics, bisphosphonates, calcium channel blockers, amiodarone, atropine, or lithium—this product has Moderate interactions with each of these categories.
The bottom line
Scorecard at a glanceFully disclosed formula with strong clinical evidence behind its ingredients' uses. Major medication interactions have been identified, and safety information is well characterized.
This is a complex multi-ingredient product with interactions affecting a broad range of common medications, including three Major-severity interactions (magnesium with levodopa/carbidopa, and green tea with nadolol, ephedrine, or atorvastatin). If you take any prescription medications, especially for blood pressure, seizures, diabetes, blood clotting, or heart rhythm, check with your own doctor or pharmacist before starting Lipo Plus.
Several ingredients lack established effectiveness for the product's stated purpose, and greater celandine carries hepatotoxicity concerns.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 11 of 16 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Apr 21, 2023.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Lipo Plus, straight from the product label.
| Brand | Priority One Nutritional Supplements |
|---|---|
| Barcode (UPC) | 815354020877 |
| Net contents | 120 Tablet(s) |
| Market status | On market |
| Date entered into DSLD | Apr 21, 2023 |
| DSLD ID | 277393 |
| Product type | Other Combinations |
| Supplement form | Tablet Or Pill |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Women (not pregnant or lactating) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for Lipo Plus by Priority One Nutritional Supplements, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Vitamin B6 | 79 mg | 4647% |
| Choline Bitartrate | 600 mg | -- |
| DL-Methionine | 600 mg | -- |
| Choline | 270 mg | 49% |
| Inositol | 600 mg | -- |
| Pituitary | 3 mg | -- |
| Duodenum | 99 mg | -- |
| Pancreatin | 300 mg | -- |
| Magnesium | 12 mg | 3% |
| Milk Thistle Seed Extract | 240 mg | -- |
| Dandelion root extract | 300 mg | -- |
| Black Radish | 150 mg | -- |
| Ox Bile | 150 mg | -- |
| Barberry | 300 mg | -- |
| Beet | 150 mg | -- |
| Celandine | 150 mg | -- |
| Green Tea | 201 mg | -- |
Other ingredients: Dicalcium Phosphate, Stearic Acid, Microcrystalline Cellulose, Silicon Dioxide, Croscarmellose Sodium, Magnesium Stearate, Methyl Cellulose
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Precautions
Warning: Contains barberry and celandine which should not be ingested by pregnant or lactating women.
Keep out of reach of children.
For professional use only.
Suggested/Recommended/Usage/Directions
Recommendations: Take (3) three tablets daily or as directed by your physician.
Storage
Keep container tightly closed, store in a cool, dry place.
General Statements
Bisphenol-A (BPA) & Phthalate Free
Seals/Symbols
GMP Certified
Brand IP Statement(s)
Priority One Nutritional Supplements Inc since 1988
FDA Statement of Identity
A Dietary Supplement
Formulation
Contains no preservatives. Non-GMO
FDA Disclaimer Statement
This statement has not been evaluated by the FDA. This product is not intended to diagnose, treat, cure, or prevent any disease.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
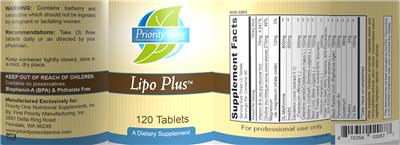
Lipo Plus by Priority One Nutritional Supplements label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Lipo Plus by Priority One Nutritional Supplements
These are the 16 active ingredients this product is made of. Select any to open its full monograph.
Serving size3 Tablet(s) Dosage formTablet Or Pill Servings per container40 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Vitamin B6
Interacts with210 drugs
Vitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is b...
Vitamin B6 monograph & interactionsDL-Methionine
Choline
Interacts with16 drugs
Choline is an essential nutrient your body needs for liver function, brain health, and nerve signaling, and many people get enough from foods like egg...
Choline monograph & interactionsInositol
Interacts with86 drugs
Inositol is a sugar alcohol made naturally in the body and found in many foods, and it is sold as a supplement (often myo-inositol) mainly for PCOS, m...
Inositol monograph & interactionsPituitary
Duodenum
Pancreatin
Magnesium
Interacts with295 drugs
Magnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preven...
Magnesium monograph & interactionsMilk Thistle Seed Extract
Interacts with954 drugs
Milk thistle is a popular herbal supplement most often used for liver health, and its main active component is a group of compounds called silymarin....
Milk Thistle Seed Extract monograph & interactionsDandelion root extract
Interacts with457 drugs
Dandelion is a common plant used in food and traditional medicine, often promoted as a natural 'water pill' and digestive aid. Human evidence for thes...
Dandelion root extract monograph & interactionsBlack Radish
Interacts with86 drugs
Radish is a common edible root vegetable that is nutritious and generally safe to eat as food. Some people use radish (especially black radish) and it...
Black Radish monograph & interactionsOx Bile
Barberry
Interacts with1,210 drugs
European barberry is a shrub whose root, bark, and berries contain berberine, a bitter plant alkaloid that has been studied mostly in isolated form. S...
Barberry monograph & interactionsBeet
Interacts with861 drugs
Beet, especially beetroot juice, is a nitrate-rich food that may modestly lower blood pressure and slightly improve exercise performance in some peopl...
Beet monograph & interactionsCelandine
Interacts with625 drugs
Greater celandine is a traditional herb most often promoted for digestive and gallbladder complaints, but solid human evidence for any use is lacking....
Celandine monograph & interactionsGreen Tea
Interacts with1,293 drugs
Green tea is a popular beverage rich in antioxidants called catechins, and drinking it in normal amounts is considered safe for most people. Concentra...
Green Tea monograph & interactionsOther (inactive) ingredients: Dicalcium Phosphate, Stearic Acid, Microcrystalline Cellulose, Silicon Dioxide, Croscarmellose Sodium, Magnesium Stearate, Methyl Cellulose. These complete the product’s ingredient list but are not active constituents.
Lipo Plus by Priority One Nutritional Supplements Drug Interactions
HelloPharmacist Interaction Report
Lipo Plus by Priority One Nutritional Supplements contains several ingredients with documented medication interactions.
The most serious concern is a Major interaction: magnesium can substantially reduce levels of levodopa/carbidopa (Sinemet), cutting the drug's bioavailability by significant amounts. This is the single highest-severity interaction in the product.
Read the full breakdown — every affected drug type, severity by severity
Beyond that, you'll encounter Moderate interactions across a wide range of drug types. Vitamin B6 can lower blood pressure additively with antihypertensive drugs, increase sun sensitivity with amiodarone, and reduce seizure-drug levels (phenobarbital and phenytoin).
Magnesium interacts with skeletal muscle relaxants (strengthening their effect), potassium-sparing diuretics, calcium channel blockers, antacids, sulfonylureas (raising blood sugar-lowering effects), quinolone antibiotics, and bisphosphonates. Milk thistle, dandelion root, black radish, barberry, beet, and greater celandine each carry Moderate interactions with antidiabetes drugs, anticoagulants or antiplatelets, cytochrome P450 substrates, and other major drug groups.
Green tea presents three Major interactions (nadolol, ephedrine, and atorvastatin) plus multiple Moderate ones with seizure medications and other drugs.
Choline bitartrate has one Minor interaction with atropine. A handful of ingredients—DL-methionine, pituitary extract, duodenum extract, pancreatin, and ox bile—could not be checked because we hold no interaction data for them.
Altogether, these interactions span 1,701 individual medications. If you take any prescription drugs, run your complete medication list through the checker below before starting this product.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Lipo Plus?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Lipo Plus interact with 1,700 drugs. Click any drug to see the details.
11 of the 16 ingredients in Lipo Plus interact with drugs. Each result below shows which ingredient is responsible. Green Tea Barberry Milk Thistle Seed Extract Beet Celandine Dandelion root extract Magnesium Vitamin B6 Inositol Black Radish Choline
Aminophylline, Amobarbital, EphedrineAmesec
How Aminophylline, Amobarbital, Ephedrine interacts with Lipo Plus — through 2 ingredients. Tap an ingredient for the detail:
Green TeaStimulant Drugs, Ephedrine Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea + Aminophylline, Amobarbital, Ephedrine interactionBarberryCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Read the full Barberry + Aminophylline, Amobarbital, Ephedrine interactionAtorvastatinAtorvaliq
How Atorvastatin interacts with Lipo Plus — through 6 ingredients. Tap an ingredient for the detail:
Green TeaHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +2 Major
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea + Atorvastatin interactionCelandineHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Celandine + Atorvastatin interactionBarberryCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, European barberry might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Barberry + Atorvastatin interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Glucuronidated Drugs +2 Moderate
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Atorvastatin interactionDandelion Root ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Atorvastatin interactionBeetCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, beet might increase the levels of CYP3A4 substrates.
Read the full Beet + Atorvastatin interactionAtorvastatin CalciumLipitor
How Atorvastatin Calcium interacts with Lipo Plus — through 6 ingredients. Tap an ingredient for the detail:
Green TeaOrganic Anion-transporting Polypeptide Substrates (oatp), Atorvastatin (lipitor) +2 Major
Interaction Summary
Theoretically, green tea might reduce the absorption of organic anion-transporting polypeptide (OATP) substrates.
Read the full Green Tea + Atorvastatin Calcium interactionDandelion Root ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Atorvastatin Calcium interactionCelandineHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Celandine + Atorvastatin Calcium interactionMilk Thistle Seed ExtractHmg-coa Reductase Inhibitors ("statins"), Organic Anion-transporting Polypeptide Substrates (oatp) +2 Moderate
Interaction Summary
Theoretically, milk thistle might interfere with statin therapy by decreasing the activity of organic anion transporting polypeptide 1B1 (OATB1B1) and inhibiting breast cancer resistance protein (BCRP).
Read the full Milk Thistle Seed Extract + Atorvastatin Calcium interactionBarberryCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, European barberry might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Barberry + Atorvastatin Calcium interactionBeetCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, beet might increase the levels of CYP3A4 substrates.
Read the full Beet + Atorvastatin Calcium interactionBendroflumethiazide, NadololCorzide
How Bendroflumethiazide, Nadolol interacts with Lipo Plus — through 4 ingredients. Tap an ingredient for the detail:
Green TeaDiuretic Drugs, Nadolol (corgard) Major
Interaction Summary
Theoretically, using green tea with diuretic drugs might increase the risk of hypokalemia.
Read the full Green Tea + Bendroflumethiazide, Nadolol interactionBarberryAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking European barberry with antihypertensive drugs might increase the risk of hypotension.
Read the full Barberry + Bendroflumethiazide, Nadolol interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Bendroflumethiazide, Nadolol interactionBeetAntihypertensive Drugs Minor
Interaction Summary
Beet and beetroot contain nitrates, which can cause vasodilation, potentially leading to lower blood pressure.
Read the full Beet + Bendroflumethiazide, Nadolol interactionBenserazide, LevodopaMadopar, Prolopa
How Benserazide, Levodopa interacts with Lipo Plus — through 2 ingredients. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Benserazide, Levodopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Benserazide, Levodopa interactionCarbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine TannateQuadratuss, Ry Tuss, Rynatuss, Tri Tannate Plus
How Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interacts with Lipo Plus — through 4 ingredients. Tap an ingredient for the detail:
Green TeaCytochrome P450 3a4 (cyp3a4) Substrates, Ephedrine +1 Major
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionBarberryAnticholinergic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, taking European barberry with anticholinergic drugs might cause additive effects.
Read the full Barberry + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionBeetCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, beet might increase the levels of CYP3A4 substrates.
Read the full Beet + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionCarbidopaLodosyn
How Carbidopa interacts with Lipo Plus — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa interactionCarbidopa, LevodopaDhivy, Rytary, Sinemet, Sinemet CR
How Carbidopa, Levodopa interacts with Lipo Plus — through 2 ingredients. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa, Levodopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Carbidopa, Levodopa interactionCarbidopa, Levodopa, EntacaponeStalevo
How Carbidopa, Levodopa, Entacapone interacts with Lipo Plus — through 4 ingredients. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa, Levodopa, Entacapone interactionDandelion Root ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Carbidopa, Levodopa, Entacapone interactionMilk Thistle Seed ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Carbidopa, Levodopa, Entacapone interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Carbidopa, Levodopa, Entacapone interactionDyphylline, Ephedrine, Guaifenesin, PhenobarbitalLufyllin-EPG
How Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interacts with Lipo Plus — through 3 ingredients. Tap an ingredient for the detail:
Green TeaStimulant Drugs, Phenobarbital (luminal) +1 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionVitamin B6Phenobarbital (luminal) Moderate
Interaction Summary
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Read the full Vitamin B6 + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionBarberryCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Read the full Barberry + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionEphedrine, Guaifenesin (otc Drug)Ephedrine Formula 400, Ephedrine Plus Tabs
How Ephedrine, Guaifenesin (otc Drug) interacts with Lipo Plus — through 1 ingredient. Tap an ingredient for the detail:
Green TeaEphedrine, Stimulant Drugs Major
Interaction Summary
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Read the full Green Tea + Ephedrine, Guaifenesin (otc Drug) interactionEphedrine, Guaifenesin, Phenobarbital, TheophyllineMudrane GG
How Ephedrine, Guaifenesin, Phenobarbital, Theophylline interacts with Lipo Plus — through 5 ingredients. Tap an ingredient for the detail:
Green TeaStimulant Drugs, Theophylline +2 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionBarberryCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Read the full Barberry + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionDandelion Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion Root Extract + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionVitamin B6Phenobarbital (luminal) Moderate
Interaction Summary
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Read the full Vitamin B6 + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionBeetCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionEphedrine, Hydroxyzine, TheophyllineAmi Rax, Marax
How Ephedrine, Hydroxyzine, Theophylline interacts with Lipo Plus — through 4 ingredients. Tap an ingredient for the detail:
Green TeaTheophylline, Ephedrine +1 Major
Interaction Summary
Theoretically, green tea might increase the levels and adverse effects of theophylline.
Read the full Green Tea + Ephedrine, Hydroxyzine, Theophylline interactionDandelion Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion Root Extract + Ephedrine, Hydroxyzine, Theophylline interactionBarberryAnticholinergic Drugs Moderate
Interaction Summary
Theoretically, taking European barberry with anticholinergic drugs might cause additive effects.
Read the full Barberry + Ephedrine, Hydroxyzine, Theophylline interactionBeetCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet + Ephedrine, Hydroxyzine, Theophylline interactionEphedrine, Phenobarbital, Potassium Iodide, TheophyllineMudrane, Quadrinal
How Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interacts with Lipo Plus — through 3 ingredients. Tap an ingredient for the detail:
Green TeaStimulant Drugs, Theophylline +2 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionBarberryCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Read the full Barberry + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionVitamin B6Phenobarbital (luminal) Moderate
Interaction Summary
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Read the full Vitamin B6 + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionEphedrine, Phenobarbital, TheophyllineTedral
How Ephedrine, Phenobarbital, Theophylline interacts with Lipo Plus — through 3 ingredients. Tap an ingredient for the detail:
Green TeaTheophylline, Phenobarbital (luminal) +2 Major
Interaction Summary
Theoretically, green tea might increase the levels and adverse effects of theophylline.
Read the full Green Tea + Ephedrine, Phenobarbital, Theophylline interactionVitamin B6Phenobarbital (luminal) Moderate
Interaction Summary
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Read the full Vitamin B6 + Ephedrine, Phenobarbital, Theophylline interactionBarberryCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Read the full Barberry + Ephedrine, Phenobarbital, Theophylline interactionEzetimibe, AtorvastatinLiptruzet
How Ezetimibe, Atorvastatin interacts with Lipo Plus — through 6 ingredients. Tap an ingredient for the detail:
Green TeaCytochrome P450 3a4 (cyp3a4) Substrates, Atorvastatin (lipitor) +2 Major
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea + Ezetimibe, Atorvastatin interactionBarberryCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, European barberry might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Barberry + Ezetimibe, Atorvastatin interactionCelandineHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Celandine + Ezetimibe, Atorvastatin interactionBeetCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, beet might increase the levels of CYP3A4 substrates.
Read the full Beet + Ezetimibe, Atorvastatin interactionDandelion Root ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Ezetimibe, Atorvastatin interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Glucuronidated Drugs +2 Moderate
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Ezetimibe, Atorvastatin interactionLevodopaInbrija, Larodopa
How Levodopa interacts with Lipo Plus — through 2 ingredients. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Levodopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Levodopa interactionLevodopa, CarbidopaDuodopa
How Levodopa, Carbidopa interacts with Lipo Plus — through 2 ingredients. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Levodopa, Carbidopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Levodopa, Carbidopa interactionNadololCorgard, Nadolol
How Nadolol interacts with Lipo Plus — through 4 ingredients. Tap an ingredient for the detail:
Green TeaNadolol (corgard) Major
Interaction Summary
Green tea seems to reduce the levels and clinical effects of nadolol.
Read the full Green Tea + Nadolol interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Nadolol interactionBarberryAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking European barberry with antihypertensive drugs might increase the risk of hypotension.
Read the full Barberry + Nadolol interactionBeetAntihypertensive Drugs Minor
Interaction Summary
Beet and beetroot contain nitrates, which can cause vasodilation, potentially leading to lower blood pressure.
Read the full Beet + Nadolol interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with Lipo Plus — through 2 ingredients. Tap an ingredient for the detail:
Green TeaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea + 6-mercaptopurine interactionCelandineImmunosuppressants, Hepatotoxic Drugs Moderate
Interaction Summary
Preliminary clinical research suggests that taking a specific semi-synthetic derivative of the greater celandine constituent chelidonine (Ukrain; not available in North America) might stimulate immune responses in cancer patients.
Read the full Celandine + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with Lipo Plus — through 4 ingredients. Tap an ingredient for the detail:
BarberryCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, European barberry might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Barberry + Ado-trastuzumab Emtansine interactionBeetCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, beet might increase the levels of CYP3A4 substrates.
Read the full Beet + Ado-trastuzumab Emtansine interactionGreen TeaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea + Ado-trastuzumab Emtansine interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with Lipo Plus — through 2 ingredients. Tap an ingredient for the detail:
CelandineHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Celandine + Abacavir Sulfate, Dolutegravir, Lamivudine interactionGreen TeaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with Lipo Plus — through 2 ingredients. Tap an ingredient for the detail:
Green TeaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea + Abacavir, Lamivudine interactionCelandineHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Celandine + Abacavir, Lamivudine interactionAbametapirXeglyze
How Abametapir interacts with Lipo Plus — through 1 ingredient. Tap an ingredient for the detail:
Green TeaCytochrome P450 1a2 (cyp1a2) Inhibitors Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Read the full Green Tea + Abametapir interactionAbciximabReoPro
How Abciximab interacts with Lipo Plus — through 4 ingredients. Tap an ingredient for the detail:
BarberryAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, European barberry may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Barberry + Abciximab interactionDandelion Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
Read the full Dandelion Root Extract + Abciximab interactionGreen TeaAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea + Abciximab interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with Lipo Plus — through 4 ingredients. Tap an ingredient for the detail:
BarberryCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, European barberry might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Barberry + Abemaciclib interactionBeetCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, beet might increase the levels of CYP3A4 substrates.
Read the full Beet + Abemaciclib interactionGreen TeaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea + Abemaciclib interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Abemaciclib interactionAbiraterone
How Abiraterone interacts with Lipo Plus — through 5 ingredients. Tap an ingredient for the detail:
BeetCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, beet might increase the levels of CYP3A4 substrates.
Read the full Beet + Abiraterone interactionGreen TeaCytochrome P450 1a2 (cyp1a2) Inhibitors, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Read the full Green Tea + Abiraterone interactionBarberryCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, European barberry might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Barberry + Abiraterone interactionCelandineHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Celandine + Abiraterone interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with Lipo Plus — through 5 ingredients. Tap an ingredient for the detail:
CelandineHepatotoxic Drugs Moderate
Interaction Summary
There is some concern that greater celandine can adversely affect the liver.
Read the full Celandine + Abiraterone Acetate interactionBarberryCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, European barberry might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Barberry + Abiraterone Acetate interactionGreen TeaHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea + Abiraterone Acetate interactionBeetCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, beet might increase the levels of CYP3A4 substrates.
Read the full Beet + Abiraterone Acetate interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with Lipo Plus — through 6 ingredients. Tap an ingredient for the detail:
Green TeaAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea + Abrocitinib interactionCelandineImmunosuppressants Moderate
Interaction Summary
Preliminary clinical research suggests that taking a specific semi-synthetic derivative of the greater celandine constituent chelidonine (Ukrain; not available in North America) might stimulate immune responses in cancer patients.
Read the full Celandine + Abrocitinib interactionBarberryAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, European barberry may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Barberry + Abrocitinib interactionDandelion Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
Read the full Dandelion Root Extract + Abrocitinib interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Abrocitinib interactionMilk Thistle Seed ExtractCytochrome P450 2c9 (cyp2c9) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP2C9; research is conflicting.
Read the full Milk Thistle Seed Extract + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with Lipo Plus — through 4 ingredients. Tap an ingredient for the detail:
BarberryCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, European barberry might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Barberry + Acalabrutinib interactionBeetCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, beet might increase the levels of CYP3A4 substrates.
Read the full Beet + Acalabrutinib interactionGreen TeaP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Green tea might increase the levels and adverse effects of P-glycoprotein (P-gp) substrates.
Read the full Green Tea + Acalabrutinib interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Acalabrutinib interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Lipo Plus with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Green Tea
Atorvastatin (Lipitor)
Green tea extract seems to reduce the levels and clinical effects of atorvastatin.
In healthy humans, taking green tea extract 300 mg or 600 mg along with atorvastatin reduces plasma levels of atorvastatin by approximately 24%. The elimination of atorvastatin is not affected. Atorvastatin is a substrate of organic anion-transporting polypeptides (OATPs). Research shows that two of the major catechins found in green tea, epicatechin gallate (ECG) and epigallocatechin gallate (EGCG), inhibit OATPs. Some OATPs are expressed in the small intestine and are responsible for the uptake of drugs and other compounds, which may have resulted in reduced plasma levels of atorvastatin. It is not clear if drinking green tea alters the absorption of atorvastatin.
Ephedrine
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Green tea contains caffeine. There is evidence that using ephedrine with caffeine might increase the risk of serious life-threatening or debilitating adverse effects such as hypertension, myocardial infarction, stroke, seizures, and death.
Nadolol (Corgard)
Green tea seems to reduce the levels and clinical effects of nadolol.
Preliminary clinical research shows that green tea consumption reduces plasma concentrations of nadolol. Compared to a control group, both peak levels and total drug exposure (AUC) of nadolol were reduced by approximately 85% in subjects who drank green tea daily for two weeks. Drinking green tea with nadolol also significantly reduced nadolol's systolic blood pressure lowering effect. Other clinical research shows that a single dose of green tea can affect plasma nadolol levels for at least one hour. Green tea catechins have been shown to inhibit organic anion transporting polypeptides (OATP), one of which, OATP1A2, is involved in the uptake of nadolol in the intestine The interaction is thought to be due primarily to the epigallocatechin gallate (EGCG) content of green tea.
5-Fluorouracil
Theoretically, high doses of green tea might increase the effects and side effects of 5-fluorouracil.
Animal research shows that taking green tea in amounts equivalent to about 6 cups daily in humans for 4 weeks prior to receiving a single injection of 5-fluorouracil increases the maximum plasma levels of 5-fluorouracil by about 2.5-fold and the area under the curve by 425%.
Adenosine (Adenocard)
Theoretically, green tea might decrease the vasodilatory effects of adenosine and interfere with its use prior to stress testing.
Green tea contains caffeine. Caffeine is a competitive inhibitor of adenosine at the cellular level. However, caffeine doesn't seem to affect supplemental adenosine because high interstitial levels of adenosine overcome the antagonistic effects of caffeine. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. However, methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Anticoagulant/Antiplatelet Drugs
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Conflicting reports exist regarding the effect of green tea on bleeding risk when used with anticoagulant or antiplatelet drugs; however, most evidence suggests that drinking green tea in moderate amounts is unlikely to cause a significant interaction. Green tea contains small amounts of vitamin K, approximately 7 mcg per cup. Some case reports have associated the antagonism of warfarin with the vitamin K content of green tea. However, these reports are rare, and very large doses of green tea (about 8-16 cups daily) appear to be needed to cause these effects. Furthermore, the catechins and caffeine in green tea are reported to have antiplatelet activity.
Beta-Adrenergic Agonists
Green tea contains caffeine. Theoretically, concomitant use of large amounts of caffeine might increase cardiac inotropic effects of beta-agonists.
Bortezomib (Velcade)
Theoretically, green tea might interfere with the effects of bortezomib.
In vitro research shows that green tea polyphenols, such as epigallocatechin gallate (EGCG), interact with bortezomib and block its proteasome inhibitory action. This prevents the induction of cell death in multiple myeloma or glioblastoma cancer cell lines. Advise patients taking bortezomib, not to take green tea.
Carbamazepine (Tegretol)
Theoretically, green tea might reduce the effects of carbamazepine and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that taking caffeine can lower the anticonvulsant effects of carbamazepine and can induce seizures when taken in doses above 400 mg/kg. Human research has shown that taking caffeine 300 mg in three divided doses along with carbamazepine 200 mg reduces the bioavailability of carbamazepine by 32% and prolongs the plasma half-life of carbamazepine 2-fold in healthy individuals.
Celiprolol (Celicard)
Theoretically, green tea might reduce the levels and clinical effects of celiprolol.
In a small human study, taking green tea daily for 4 days appears to decrease blood and urine levels of celiprolol by at least 98%. This interaction is possibly due to the inhibition of organic anion transporting polypeptide (OATP). Green tea catechins have been shown to inhibit organic anion transporting polypeptides (OATP), one of which, OATP1A2, is found in the intestine The interaction is thought to be due primarily to the epigallocatechin gallate (EGCG) content of green tea.
Cimetidine (Tagamet)
Theoretically, concomitant use might increase the effects and adverse effects of caffeine in green tea.
Green tea contains caffeine. Cimetidine can reduce caffeine clearance by 31% to 42%.
Clozapine (Clozaril)
Theoretically, green tea might increase the levels and adverse effects of clozapine and acutely exacerbate psychotic symptoms.
Animal research suggests that, although green tea extract does not affect the elimination of clozapine, it delays the time to reach peak concentration and reduces the peak plasma levels. Also, concomitant administration of green tea and clozapine might theoretically cause acute exacerbation of psychotic symptoms due to the caffeine in green tea. Caffeine can increase the effects and toxicity of clozapine. Caffeine doses of 400-1000 mg daily inhibit clozapine metabolism. Clozapine is metabolized by cytochrome P450 1A2 (CYP1A2). Researchers speculate that caffeine might inhibit CYP1A2. However, there is no reliable evidence that caffeine affects CYP1A2. There is also speculation that genetic factors might make some patients be more sensitive to the interaction between clozapine and caffeine.
Contraceptive Drugs
Theoretically, concomitant use might increase the effects and adverse effects of caffeine found in green tea.
Green tea contains caffeine. Oral contraceptives can decrease caffeine clearance by 40% to 65%.
Cytochrome P450 1A2 (Cyp1A2) Inhibitors
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Caffeine is metabolized by cytochrome P450 1A2 (CYP1A2),. Theoretically, drugs that inhibit CYP1A2 may decrease the clearance rate of caffeine from green tea and increase caffeine levels.
Dipyridamole (Persantine)
Theoretically, green tea might decrease the vasodilatory effects of dipyridamole and interfere with its use prior to stress testing.
Green tea contains caffeine. Caffeine might inhibit dipyridamole-induced vasodilation. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. Methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Disulfiram (Antabuse)
Theoretically, disulfiram might increase the risk of adverse effects from caffeine.
In human research, disulfiram decreases the clearance and increases the half-life of caffeine.
Diuretic Drugs
Theoretically, using green tea with diuretic drugs might increase the risk of hypokalemia.
Green tea contains caffeine. In excessive amounts, caffeine can reduce potassium levels due to stimulation of the sodium-potassium pump. Diuretics can also cause lower potassium levels.
Estrogens
Theoretically, estrogens might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Estrogen inhibits caffeine metabolism.
Ethosuximide (Zarontin)
Theoretically, green tea might reduce the effects of ethosuximide and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that caffeine 92.4 mg/kg can decrease the anticonvulsant activity of ethosuximide. However, this effect has not been reported in humans.
Felbamate (Felbatol)
Theoretically, green tea might reduce the effects of felbamate and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that a high dose of caffeine 161.7 mg/kg can decreases the anticonvulsant activity of felbamate. However, this effect has not been reported in humans.
Fexofenadine (Allegra)
Green tea can decrease blood levels of fexofenadine.
Clinical research shows that green tea can significantly decrease blood levels and excretion of fexofenadine. Taking green tea extract with a dose of fexofenadine decreased bioavailability of fexofenadine by about 30%. In vitro, green tea inhibits the cellular accumulation of fexofenadine by inhibiting the organic anion transporting polypeptide (OATP) drug transporter. Research shows that two of the major catechins found in green tea, epicatechin gallate (ECG) and epigallocatechin gallate (EGCG), inhibit OATPs, specifically OATP1A2, OATP1B1, and OATP2B1. In addition, green tea has been shown to reduce the absorption of some drugs that are OATP substrates.
Flutamide (Eulexin)
Theoretically, green tea might increase the levels and adverse effects of flutamide.
Green tea contains caffeine. In vitro evidence suggests that caffeine can inhibit the metabolism of flutamide. Theoretically, concomitant use of caffeine and flutamide might increase serum concentrations of flutamide and increase the risk adverse effects.
Fluvoxamine (Luvox)
Theoretically, fluvoxamine might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Fluvoxamine reduces caffeine metabolism.
Hepatotoxic Drugs
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Green tea extract supplements have been linked to several cases of hepatotoxicity and might have additive hepatotoxic effects with other drugs..
Imatinib (Gleevec)
Theoretically, green tea might reduce the levels and clinical effects of imatinib.
In animal research, a single dose of green tea extract reduces the area under the curve (AUC) of imatinib by up to approximately 64% and its main metabolite N-desmethyl imatinib by up to approximately 81%. This interaction has not been shown in humans. The mechanism of action is unclear but may involve multiple pathways.
Barberry
Anticholinergic Drugs
Theoretically, taking European barberry with anticholinergic drugs might cause additive effects.
In vitro evidence suggests that European barberry might have anticholinergic properties.
Anticoagulant/Antiplatelet Drugs
Theoretically, European barberry may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro and animal evidence suggest that berberine, a constituent of European barberry, might inhibit platelet aggregation. Theoretically, European barberry might have a similar effect.
Antidiabetes Drugs
Theoretically, taking European barberry with antidiabetes drugs might increase the risk of hypoglycemia.
Preliminary clinical evidence suggests that European barberry juice reduces fasting glucose levels in patients with type 2 diabetes who are also taking antidiabetes drugs. Additionally, some animal studies show that berberine, a constituent of European barberry, has antiglycemic potential. Monitor blood glucose levels closely.
Antihypertensive Drugs
Theoretically, taking European barberry with antihypertensive drugs might increase the risk of hypotension.
Animal and human research suggests that European barberry extracts can have hypotensive effects.
Cholinergic Drugs
Theoretically, taking European barberry with cholinergic drugs might decrease the effects of cholinergic drugs.
In vitro evidence suggests that European barberry might have anticholinergic properties.
Cns Depressants
Theoretically, concomitant use with drugs that have sedative properties may cause additive effects.
Animal research suggests that berberine, a constituent of European barberry, might have sedative effects. Theoretically, European barberry might have a similar effect.
Cyclosporine (Neoral, Sandimmune)
Theoretically, concomitant use with cyclosporine may cause additive effects.
Berberine, a constituent of European barberry, can reduce the metabolism and increase serum levels of cyclosporine. This effect is attributed to the ability of berberine to inhibit cytochrome P450 3A4 (CYP3A4), which metabolizes cyclosporine. Theoretically, European barberry might have a similar effect.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, European barberry might increase the levels and clinical effects of CYP3A4 substrates.
There is very preliminary evidence suggesting that berberine, a constituent of European barberry, might inhibit the CYP3A4 enzyme. Theoretically, European barberry might have a similar effect.
Milk Thistle Seed Extract
Antidiabetes Drugs
Taking milk thistle with antidiabetes drugs may increase the risk of hypoglycemia.
Clinical research shows that milk thistle extract, alone or along with tree turmeric extract, can lower blood glucose levels and glycated hemoglobin (HbA1c) in patients with type 2 diabetes, including those already taking antidiabetes drugs. Additionally, animal research shows that milk thistle extract increases the metformin maximum plasma concentration and area under the curve and decreases the renal clearance of metformin, due to inhibition of the multi-drug and toxin extrusion protein 1 (MATE1) renal tubular transport protein.
Cytochrome P450 2B6 (Cyp2B6) Substrates
Theoretically, milk thistle might inhibit CYP2B6.
An in vitro study shows that silybin, a constituent of milk thistle, binds to and noncompetitively inhibits CYP2B6. Additionally, silybin might downregulate the expression of CYP2B6 by decreasing mRNA and protein levels.
Glucuronidated Drugs
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Laboratory research shows that milk thistle constituents inhibit uridine diphosphoglucuronosyl transferase (UGT), the major phase 2 enzyme that is responsible for glucuronidation. Theoretically, this could decrease the clearance and increase levels of glucuronidated drugs. Other laboratory research suggests that a milk thistle extract of silymarin might inhibit beta-glucuronidase, although the significance of this effect is unclear.
Ledipasvir
Theoretically, milk thistle might increase the levels and clinical effects of ledipasvir.
Animal research in rats shows that milk thistle increases the area under the curve (AUC) for ledipasvir and slows its elimination.
Morphine
Theoretically, concomitant use of milk thistle with morphine might affect serum levels of morphine and either increase or decrease its effects.
Animal research shows that milk thistle reduces serum levels of morphine by up to 66%. In contrast, laboratory research shows that milk thistle constituents inhibit uridine diphosphoglucuronosyl transferase (UGT), the major phase 2 enzyme that is responsible for glucuronidation. Theoretically, this could decrease the clearance and increase morphine levels. The effect of taking milk thistle on morphine metabolism in humans is not known.
Raloxifene (Evista)
Theoretically, milk thistle might decrease the clearance and increase levels of raloxifene.
Laboratory research suggests that the milk thistle constituents silibinin and silymarin inhibit the glucuronidation of raloxifene in the intestines.
Sirolimus (Rapamune)
Milk thistle might decrease the clearance of sirolimus.
Pharmacokinetic research shows that a milk thistle extract of silymarin decreases the apparent clearance of sirolimus in hepatically impaired renal transplant patients. It is unclear if this interaction occurs in patients without hepatic impairment.
Sofosbuvir (Solvaldi)
Theoretically, milk thistle might decrease the levels and clinical effects of sofosbuvir.
Animal research in rats shows that milk thistle reduces the metabolism of sofosbuvir, as well as the hepatic uptake of its active metabolite.
Tamoxifen (Nolvadex)
Theoretically, the milk thistle constituent silibinin might increase tamoxifen levels and interfere with its conversion to an active metabolite.
Animal research suggests that the milk thistle constituent silibinin might increase plasma levels of tamoxifen and alter its conversion to an active metabolite. The mechanism appears to involve inhibition of pre-systemic metabolism of tamoxifen by cytochrome P450 (CYP) 2C9 and CYP3A4, and inhibition of P-glycoprotein-mediated efflux of tamoxifen into the intestine for excretion. Whether this interaction occurs in humans is not known.
Warfarin (Coumadin)
Theoretically, milk thistle might increase the effects of warfarin.
In one case report, a man stabilized on warfarin experienced an increase in INR from 2.64 to 4.12 after taking a combination product containing milk thistle 200 mg daily, as well as dandelion, wild yam, niacinamide, and vitamin B12. Levels returned to normal after stopping the supplement. Although a direct correlation between milk thistle and the change in INR cannot be confirmed, some in vitro research suggests that milk thistle might inhibit cytochrome P450 2C9 (CYP2C9), an enzyme involved in the metabolism of various drugs, including warfarin.
Cytochrome P450 2C9 (Cyp2C9) Substrates
It is unclear if milk thistle inhibits CYP2C9; research is conflicting.
In vitro research suggests that milk thistle might inhibit CYP2C9. Additionally, 3 case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking milk thistle and cancer medications that are CYP2C9 substrates, including imatinib and capecitabine. However, contradictory clinical research shows that milk thistle extract does not inhibit CYP2C9 or significantly affect levels of the CYP2C9 substrate tolbutamide. Differences in results could be due to differences in dosages or formulations utilized.
Cytochrome P450 3A4 (Cyp3A4) Substrates
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
While laboratory research shows conflicting results, pharmacokinetic research shows that taking milk thistle extract 420-1350 mg daily does not significantly affect the metabolism of the CYP3A4 substrates irinotecan, midazolam, or indinavir. However, 8 case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking milk thistle and cancer medications that are CYP3A4 substrates, including gefitinib, sorafenib, doxorubicin, and vincristine.
Estrogens
Theoretically, milk thistle might interfere with estrogen therapy through competition for estrogen receptors.
Animal research suggests that a milk thistle extract of silymarin binds to estrogen receptor beta.
Hmg-Coa Reductase Inhibitors ("Statins")
Theoretically, milk thistle might interfere with statin therapy by decreasing the activity of organic anion transporting polypeptide 1B1 (OATB1B1) and inhibiting breast cancer resistance protein (BCRP).
Preliminary evidence suggests that a milk thistle extract of silymarin can decrease the activity of the OATP1B1, which transports HMG-CoA reductase inhibitors into the liver to their site of action, and animal research shows this increases the maximum plasma concentration of pitavastatin and pravastatin. The silibinin component also inhibits BCRP, which transports statins from the liver into the bile for excretion. However, in a preliminary study in healthy males, silymarin 140 mg three times daily had no effect on the pharmacokinetics of a single 10 mg dose of rosuvastatin.
Indinavir (Crixivan)
Theoretically, milk thistle may induce cytochrome P450 3A4 (CYP3A4) enzymes and increase the metabolism of indinavir; however, results are conflicting.
One pharmacokinetic study shows that taking milk thistle (Standardized Milk Thistle, General Nutrition Corp.) 175 mg three times daily in combination with multiple doses of indinavir 800 mg every 8 hours decreases the mean trough levels of indinavir by 25%. However, results from the same pharmacokinetic study show that milk thistle does not affect the overall exposure to indinavir. Furthermore, two other pharmacokinetic studies show that taking specific milk thistle extract (Legalon, Rottapharm Madaus; Thisilyn, Nature's Way) 160-450 mg every 8 hours in combination with multiple doses of indinavir 800 mg every 8 hours does not reduce levels of indinavir.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Milk thistle may inhibit one form of OATP, OATP-B1, which could reduce the bioavailability and clinical effects of OATP-B1 substrates.
In vitro research shows that milk thistle inhibits OATP-B1. Two case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking milk thistle and cancer medications that are OATP substrates, including sorafenib and methotrexate. OATPs are expressed in the small intestine and liver and are responsible for the uptake of drugs and other compounds into the body. Inhibition of OATP may reduce the bioavailability of oral drugs that are substrates of OATP.
P-Glycoprotein Substrates
Theoretically, milk thistle might increase the absorption of P-glycoprotein substrates. However, this effect does not seem to be clinically significant.
In vitro research shows that milk thistle can inhibit P-glycoprotein activity and 1 case report from the World Health Organization (WHO) adverse drug reaction database describes increased abdominal pain in a patient taking milk thistle and the cancer medication vincristine, a P-glycoprotein substrate, though this patient was also taking methotrexate. However, a small pharmacokinetic study in healthy volunteers shows that taking milk thistle (Enzymatic Therapy Inc.) 900 mg, standardized to 80% silymarin, in 3 divided doses daily for 14 days does not affect absorption of digoxin, a P-glycoprotein substrate.
Beet
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, beet might increase the levels of CYP3A4 substrates.
In vitro research suggests that betanin, the major pigment in beet, competitively inhibits CYP3A4 in a dose-dependent manner similarly to strong CYP3A4 inhibitor ketoconazole.
Antihypertensive Drugs
Beet and beetroot contain nitrates, which can cause vasodilation, potentially leading to lower blood pressure. However, a study published in the European Journal of Clinical Nutrition using concentrated beetroot juice found no significant impact on blood pressure or heart rate in different age groups. Other small clinical studies suggest that while beet consumption might transiently lower blood pressure due to vessel dilation, there's no consistent evidence of a lasting effect. Overall, the theoretical risk of reduced blood pressure due to beet's nitrate content exists, but studies generally indicate a low and temporary impact rather than a sustained decrease.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
In vitro research suggests that beet induces CYP1A2 enzymes.
Celandine
Cytochrome P450 2D6 (Cyp2D6) Substrates
Research in vitro shows that chelidonine, a constituent of greater celandine, inhibits cytochrome P450 2D6 (CYP2D6) enzyme activity. Theoretically, greater celandine might increase levels of drugs metabolized by CYP2D6.
Some drugs metabolized by CYP2D6 include amitriptyline (Elavil), clozapine (Clozaril), codeine, desipramine (Norpramin), donepezil (Aricept), fentanyl (Duragesic), flecainide (Tambocor), fluoxetine (Prozac), meperidine (Demerol), methadone (Dolophine), metoprolol (Lopressor, Toprol XL), olanzapine (Zyprexa), ondansetron (Zofran), tramadol (Ultram), trazodone (Desyrel), and many others.
Hepatotoxic Drugs
There is some concern that greater celandine can adversely affect the liver. Greater celandine has been linked to many cases of hepatotoxicity. Theoretically, concomitant use with other potentially hepatotoxic drugs might increase the risk of developing liver damage. Some of these drugs include acarbose (Precose, Prandase), amiodarone (Cordarone), atorvastatin (Lipitor), azathioprine (Imuran), carbamazepine (Tegretol), cerivastatin (Baycol), diclofenac (Voltaren), felbamate (Felbatol), fenofibrate (TriCor), fluvastatin (Lescol), gemfibrozil (Lopid), isoniazid, itraconazole, (Sporanox), ketoconazole (Nizoral), leflunomide (Arava), lovastatin (Mevacor), methotrexate (Rheumatrex), nevirapine (Viramune), niacin, nitrofurantoin (Macrodantin), pioglitazone (Actos), pravastatin (Pravachol), pyrazinamide, rifampin (Rifadin), ritonavir (Norvir), rosiglitazone (Avandia), simvastatin (Zocor), tacrine (Cognex), tamoxifen, terbinafine (Lamisil), valproic acid, and zileuton (Zyflo).
Immunosuppressants
Preliminary clinical research suggests that taking a specific semi-synthetic derivative of the greater celandine constituent chelidonine (Ukrain; not available in North America) might stimulate immune responses in cancer patients. Theoretically, taking greater celandine might decrease the effects of immunosuppressive therapy. Immunosuppressant drugs include azathioprine (Imuran), basiliximab (Simulect), cyclosporine (Neoral, Sandimmune), daclizumab (Zenapax), muromonab-CD3 (OKT3, Orthoclone OKT3), mycophenolate (CellCept), tacrolimus (FK506, Prograf), sirolimus (Rapamune), prednisone (Deltasone, Orasone), and other corticosteroids (glucocorticoids).
Monoamine Oxidase Inhibitors (Maois)
Theoretically taking monoamine oxidase inhibitors (MAOIs) with greater celandine might increase the risk of serotonergic side effects including serotonin syndrome. In vitro research shows that chelerythrine, an isoquinoline alkaloid in greater celandine, strongly, selectively, and reversibly inhibits an isoform of recombinant human monoamine oxidase-A (MAO-A). It was also a weak but selective inhibitor of monoamine oxidase-B (MAO-B). Some MAOIs include phenelzine (Nardil), tranylcypromine (Parnate), and others.
Dandelion root extract
Anticoagulant/Antiplatelet Drugs
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
In vitro research suggests that dandelion root inhibits platelet aggregation.
Antidiabetes Drugs
Theoretically, dandelion might increase the risk for hypoglycemia when used with antidiabetes drugs.
Laboratory research suggests that dandelion extract may have moderate alpha-glucosidase inhibitor activity and might also increase insulin secretion. Also, in a case report, a 58-year-old woman with type 2 diabetes who was being treated with insulin developed hypoglycemia 2 weeks after beginning to eat salads containing dandelion.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Laboratory research suggests that dandelion might inhibit CYP1A2. So far, this interaction has not been reported in humans. However, until more is known, watch for an increase in the levels of drugs metabolized by CYP1A2 in patients taking dandelion.
Glucuronidated Drugs
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
There is some preliminary evidence that dandelion might induce UDP-glucuronosyltransferase, a phase II enzyme.
Lithium
Theoretically, through diuretic effects, dandelion might reduce excretion and increase levels of lithium.
Animal research suggests that dandelion has diuretic properties. As diuretics can increase serum lithium levels, the dose of lithium might need to be decreased when taken with dandelion.
Potassium-Sparing Diuretics
Theoretically, dandelion might increase the risk of hyperkalemia when taken with potassium-sparing diuretics.
Dandelion contains significant amounts of potassium.
Quinolone Antibiotics
Theoretically, dandelion might lower fluoroquinolone levels.
Animal research shows that dandelion reduces absorption of ciprofloxacin and can lower levels by 73%. However, this effect has not been reported in humans.
Magnesium
Levodopa/Carbidopa (Sinemet)
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Clinical research in healthy volunteers shows that taking magnesium oxide 1000 mg with levodopa 100 mg/carbidopa 10 mg reduces the area under the curve (AUC) of levodopa by 35% and of carbidopa by 81%. In vitro and animal research shows that magnesium produces an alkaline environment in the digestive tract, which might lead to degradation and reduced bioavailability of levodopa/carbidopa.
Aminoglycoside Antibiotics
Concomitant use of aminoglycoside antibiotics and magnesium can increase the risk for neuromuscular weakness.
Both aminoglycosides and magnesium reduce presynaptic acetylcholine release, which can lead to neuromuscular blockade and possible paralysis. This is most likely to occur with high doses of magnesium given intravenously.
Antacids
Use of acid reducers may reduce the laxative effect of magnesium oxide.
A retrospective analysis shows that, in the presence of H2 receptor antagonists (H2RAs) or proton pump inhibitors (PPIs), a higher dose of magnesium oxide is needed for a laxative effect. This may also occur with antacids. Under acidic conditions, magnesium oxide is converted to magnesium chloride and then to magnesium bicarbonate, which has an osmotic laxative effect. By reducing acidity, antacids may reduce the conversion of magnesium oxide to the active bicarbonate salt.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after magnesium containing products.
Bisphosphonates
Magnesium can decrease absorption of bisphosphonates.
Cations, including magnesium, can decrease bisphosphonate absorption. Advise patients to separate doses of magnesium and these drugs by at least 2 hours.
Calcium Channel Blockers
Magnesium can have additive effects with calcium channel blockers, although evidence is conflicting.
Magnesium inhibits calcium entry into smooth muscle cells and may therefore have additive effects with calcium channel blockers. Severe hypotension and neuromuscular blockades may occur when nifedipine is used with intravenous magnesium, although some contradictory evidence suggests that concurrent use of magnesium with nifedipine does not increase the risk of neuromuscular weakness. High doses of magnesium could theoretically have additive effects with other calcium channel blockers.
Digoxin
Magnesium salts may reduce absorption of digoxin.
Clinical evidence suggests that treatment with oral magnesium hydroxide or magnesium trisilicate reduces absorption of digoxin from the intestines. This may reduce the blood levels of digoxin and decrease its therapeutic effects.
Potassium-Sparing Diuretics
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Potassium-sparing diuretics also have magnesium-sparing properties, which can counteract the magnesium losses associated with loop and thiazide diuretics. Theoretically, increased magnesium levels could result from concomitant use of potassium-sparing diuretics and magnesium supplements.
Quinolone Antibiotics
Magnesium decreases absorption of quinolones.
Magnesium can form insoluble complexes with quinolones and decrease their absorption. Advise patients to take these drugs at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Skeletal Muscle Relaxants
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Parenteral magnesium shortens the time to onset of skeletal muscle relaxants by about 1 minute and prolongs the duration of action by about 2 minutes. Magnesium potentiates the effects of skeletal muscle relaxants by decreasing calcium-mediated release of acetylcholine from presynaptic nerve terminals, reducing postsynaptic sensitivity to acetylcholine, and having a direct effect on the membrane potential of myocytes. Magnesium also has vasodilatory actions and increases cardiac output, allowing a greater amount of muscle relaxant to reach the motor end plate. A clinical study found that low-dose rocuronium (0.45 mg/kg), when given after administration of magnesium 30 mg/kg over 10 minutes, has an accelerated onset of effect, which matches the onset of effect seen with a full-dose rocuronium regimen (0.6 mg/kg). In another clinical study, onset times for rocuronium doses of 0.3, 0.6, and 1.2 mg/kg were 86, 76, and 50 seconds, respectively, when given alone, but were reduced to 66, 44, and 38 seconds, respectively, when the doses were given after a 15-minute infusion of magnesium sulfate 60 mg/kg. Giving intraoperative intravenous magnesium sulfate, 50 mg/kg loading dose followed by 15 mg/kg/hour, reduces the onset time of rocuronium, enhances its clinical effects, reduces the dose of intraoperative opiates, and prolongs the spontaneous recovery time. It does not affect the activity of subsequently administered neostigmine.
Sulfonylureas
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Clinical research shows that administration of magnesium hydroxide with glyburide increases glyburide absorption, increases maximal insulin response by 35-fold, and increases the risk of hypoglycemia, when compared with glyburide alone. A similar interaction occurs between magnesium hydroxide and glipizide. The mechanism of this effect appears to be related to the elevation of gastrointestinal pH by magnesium-based antacids, increasing solubility and enhancing absorption of sulfonylureas.
Tetracycline Antibiotics
Magnesium decreases absorption of tetracyclines.
Magnesium can form insoluble complexes with tetracyclines in the gut and decrease their absorption and antibacterial activity. Advise patients to take these drugs 1 hour before or 2 hours after magnesium supplements.
Anticoagulant/Antiplatelet Drugs
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
In vitro evidence shows that magnesium sulfate inhibits platelet aggregation, even at low concentrations. Some preliminary clinical evidence shows that infusion of magnesium sulfate increases bleeding time by 48% and reduces platelet activity. However, other clinical research shows that magnesium does not affect platelet aggregation, although inhibition of platelet-dependent thrombosis can occur.
Gabapentin (Neurontin)
Gabapentin absorption can be decreased by magnesium.
Clinical research shows that giving magnesium oxide orally along with gabapentin decreases the maximum plasma concentration of gabapentin by 33%, time to maximum concentration by 36%, and area under the curve by 43%. Advise patients to take gabapentin at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Sevelamer (Renagel, Renvela)
Sevelamer may increase serum magnesium levels.
In patients on hemodialysis, sevelamer use was associated with a 0.28 mg/dL increase in serum magnesium. The mechanism of this interaction remains unclear.
Vitamin B6
Amiodarone (Cordarone)
Theoretically, vitamin B6 might increase the photosensitivity caused by amiodarone.
Despite initial case reports suggesting that pyridoxine may have a protective effect against amiodarone-induced photosensitivity, preliminary clinical research suggests that pyridoxine may actually exacerbate this adverse effect.
Antihypertensive Drugs
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Research in hypertensive rats shows that vitamin B6 can decrease systolic blood pressure. Similarly, clinical research in patients with hypertension shows that taking high doses of vitamin B6 may reduce systolic and diastolic blood pressure, possibly by reducing plasma levels of epinephrine and norepinephrine.
Phenobarbital (Luminal)
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenobarbital, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenobarbital to avoid high doses of vitamin B6.
Phenytoin (Dilantin)
High doses of vitamin B6 may reduce the levels and clinical effects of phenytoin.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenytoin, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenytoin to avoid high doses of vitamin B6.
Levodopa
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Vitamin B6 (pyridoxine) enhances the metabolism of levodopa, reducing its clinical effects. However, this interaction does not occur when carbidopa is used concurrently with levodopa (Sinemet). Therefore, it is not likely to be a problem in most people.
Inositol
Antidiabetes Drugs
Theoretically, taking inositol with antidiabetes drugs might increase the risk of hypoglycemia.
Clinical research shows that inositol lowers blood glucose levels and glycated hemoglobin (HbA1c) levels in patients with diabetes.
Black Radish
Antidiabetes Drugs
Theoretically, radish might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Animal research shows that radish extract, juice, and sprouts can reduce glucose levels. Animal research also shows that radish root juice 300 mg/kg reduces fasting and postprandial blood glucose in a rat model of diabetes, with effects similar to glibenclamide.
Choline
Atropine
Theoretically, choline might decrease the effects of atropine in the brain.
Animal research shows that administering choline one hour before administering atropine can attenuate atropine-induced decreases in brain levels of acetylcholine. Theoretically, concomitant use of choline and atropine may decrease the effects of atropine.
Brand information
Manufacturer and brand details for Lipo Plus, from the product label.
Priority One Nutritional Supplements
See all Priority One Nutritional Supplements products- Name
- Priority One Nutritional Supplements, Inc.
- Web Address
- www.priorityonevitamins.com
Lipo Plus by Priority One Nutritional Supplements: Common Questions
Does Lipo Plus by Priority One Nutritional Supplements interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take Lipo Plus while I'm pregnant?
What does the green tea in this product do?
Is magnesium in this product safe?
What's milk thistle supposed to help with?
Can I breastfeed while taking Lipo Plus?
Does this product actually work for what it claims?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Lipo Plus is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Lipo Plus’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin B6
Interacts with 210 drugsVitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is best known for helping with pregnancy-rel...
Read the full Vitamin B6 monograph → Herb & supplement monographCholine
Interacts with 16 drugsCholine is an essential nutrient your body needs for liver function, brain health, and nerve signaling, and many people get enough from foods like eggs, meat, and fish. Supplements may help...
Read the full Choline monograph → Herb & supplement monographInositol
Interacts with 86 drugsInositol is a sugar alcohol made naturally in the body and found in many foods, and it is sold as a supplement (often myo-inositol) mainly for PCOS, mood, and metabolic concerns. The stronge...
Read the full Inositol monograph → Herb & supplement monographMagnesium
Interacts with 295 drugsMagnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preventing or correcting deficiency. Some othe...
Read the full Magnesium monograph → Herb & supplement monographMilk Thistle
Interacts with 954 drugsMilk thistle is a popular herbal supplement most often used for liver health, and its main active component is a group of compounds called silymarin. While it is generally well tolerated, th...
Read the full Milk Thistle monograph → Herb & supplement monographDandelion
Interacts with 457 drugsDandelion is a common plant used in food and traditional medicine, often promoted as a natural 'water pill' and digestive aid. Human evidence for these uses is very limited, so its benefits...
Read the full Dandelion monograph → Herb & supplement monographRadish
Interacts with 86 drugsRadish is a common edible root vegetable that is nutritious and generally safe to eat as food. Some people use radish (especially black radish) and its extracts for digestion and liver suppo...
Read the full Radish monograph → Herb & supplement monographEuropean Barberry
Interacts with 1,210 drugsEuropean barberry is a shrub whose root, bark, and berries contain berberine, a bitter plant alkaloid that has been studied mostly in isolated form. Some early research on berberine is promi...
Read the full European Barberry monograph → Herb & supplement monographBeet
Interacts with 861 drugsBeet, especially beetroot juice, is a nitrate-rich food that may modestly lower blood pressure and slightly improve exercise performance in some people. It is generally safe as a food, but s...
Read the full Beet monograph → Herb & supplement monographGreater Celandine
Interacts with 625 drugsGreater celandine is a traditional herb most often promoted for digestive and gallbladder complaints, but solid human evidence for any use is lacking. More importantly, it has been linked to...
Read the full Greater Celandine monograph → Herb & supplement monographGreen Tea
Interacts with 1,293 drugsGreen tea is a popular beverage rich in antioxidants called catechins, and drinking it in normal amounts is considered safe for most people. Concentrated green tea extracts are a different s...
Read the full Green Tea monograph →Sources & How We Checked
Lipo Plus's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 516 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Vitamin B6 32 references
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Geerling BJ, Dagnelie PC, Badart-Smook A, et al. Diet as a risk factor for the development of ulcerative colitis. Am J Gastroenterol 2000;95:1008-13. PubMed
- South M. Neonatal seizures after pyridoxine use -- reply. Lancet 1999;354:2083. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Baxter P, Aicardi J. Neonatal seizures after pyridoxine use. Lancet 1999;354:2082-3. PubMed
- Bendich A, Cohen M. Vitamin B6 safety issues. Ann N Y Acad Sci 1990;585:321-30.
- Schaumburg H, Kaplan J, Windebank A. Sensory neuropathy from pyridoxine abuse. A new megavitamin syndrome. N Engl J Med 1983;309:445-8. PubMed
- Gordon N. Pyridoxine dependency: an update. Dev Med Child Neurol 1997;39:63-5. PubMed
- Lewis PJ. Pain in the hand and wrist. Pyridoxine supplements may help patients with carpal tunnel syndrome. BMJ 1995;310:1534. PubMed
- Kaufman G. Pyridoxine against amiodarone-induced photosensitivity (letter). Lancet 1984;1:51-2. PubMed
- Mulrow JP, Mulrow CD, McKenna WJ. Pyridoxine and amiodarone-induced photosensitivity. Ann Intern Med 1985;103:68-9. PubMed
- Kawada A, Kashima A, Shiraishi H, et al. Pyridoxine-induced photosensitivity and hypophosphatasia. Dermatology 2000;201:356-60.. PubMed
- Vasile A, Goldberg R, Kornberg B. Pyridoxine toxicity: report of a case. J Am Osteopath Assoc 1984;83:790-1. DOI
- Hansson O, Sillanpaa M. Pyridoxine and serum concentration of phenytoin and phenobarbitone. Lancet 1976;1:256. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Chittumma P, Kaewkiattikun K, Wiriyasiriwach B. Comparison of the effectiveness of ginger and vitamin B6 for treatment of nausea and vomiting in early pregnancy: a randomized double-blind controlled trial. J Med Assoc Thai 2007;90:15-20.
- Hatzitolios, A., Iliadis, F., Katsiki, N., and Baltatzi, M. Is the anti-hypertensive effect of dietary supplements via aldehydes reduction evidence based? A systematic review. Clin Exp.Hypertens. 2008;30(7):628-639. PubMed
- Vasdev, S., Ford, C. A., Parai, S., Longerich, L., and Gadag, V. Dietary vitamin B6 supplementation attenuates hypertension in spontaneously hypertensive rats. Mol.Cell Biochem. 1999;200(1-2):155-162.
- de, Vogel S., Dindore, V., van, Engeland M., Goldbohm, R. A., van den Brandt, P. A., and Weijenberg, M. P. Dietary folate, methionine, riboflavin, and vitamin B-6 and risk of sporadic colorectal cancer. J Nutr 2008;138(12):2372-2378. PubMed
- Hagen, I., Nesheim, B. I., and Tuntland, T. No effect of vitamin B-6 against premenstrual tension. A controlled clinical study. Acta Obstet.Gynecol.Scand. 1985;64(8):667-670. PubMed
- Aybak, M., Sermet, A., Ayyildiz, M. O., and Karakilcik, A. Z. Effect of oral pyridoxine hydrochloride supplementation on arterial blood pressure in patients with essential hypertension. Arzneimittelforschung. 1995;45(12):1271-1273.
- Lal, K. J., Dakshinamurti, K., and Thliveris, J. The effect of vitamin B6 on the systolic blood pressure of rats in various animal models of hypertension. J Hypertens. 1996;14(3):355-363. PubMed
- Lauritzen CH, Reuter HD, Repges R, Bohnert K, and Schmidt U. Treatment of premenstrual tension syndrome with Vitex agnus castus. Controlled, double-blind study versus pyridoxine. Phytomed 1997;4(3):183-189. PubMed
- Fonseca VA, Lavery LA, Thethi TK, et al. Metanx in type 2 diabetes with peripheral neuropathy: A randomized trial. Am J Med 2013;126(2):141-9. PubMed
- Hankey GJ, Eikelboom JW, Yi Q, et al. Treatment with B vitamins and incidence of cancer in patients with previous stroke or transient ischemic attack: Results of a randomized placebo-controlled trial. Stroke 2012;43(6):1572-7. PubMed
- Hoyer-Kuhn H, Kohbrok S, Volland R, Franklin J, Hero B, Beck BB, Hoppe B. Vitamin B6 in primary hyperoxaluria I: first prospective trial after 40 years of practice. Clin J Am Soc Nephrol. 2014 Mar;9(3):468-77. PubMed
- Mahmoud A, Tabassum S, Al Enazi S, et al. Amelioration of levetiracetam-induced behavioral side effects by pyridoxine. A randomized double blind controlled study. Pediatr Neurol 2021;119:15-21. PubMed
- Gupta M, Gallante B, Bamberger JN, et al. Prospective randomized evaluation of idiopathic hyperoxaluria treatments. J Endourol 2021;35(12):1844-1851. PubMed
- Li H, Chen M, Liang S, et al. Excessive vitamin B6 during treatment is related to poor prognosis of patients with nasopharyngeal carcinoma: A U-shaped distribution suggests low dose supplement. Clin Nutr 2021;40(4):2293-2300. PubMed
- Tanigawa J, Nabatame S, Tominaga K, et al. High-dose pyridoxine treatment for inherited glycosylphosphatidylinositol deficiency. Brain Dev 2021;43(6):680-687. PubMed
- Committee on Practice Bulletins-Obstetrics. ACOG Practice Bulletin No. 189: Nausea And Vomiting Of Pregnancy. Obstet Gynecol. 2018;131(1):e15-e30. PubMed
Choline 14 references
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Cho E, Willett WC, Colditz GA, et al. Dietary choline and betaine and the risk of distal colorectal adenoma in women. J Natl Cancer Inst 2007;99:1224-31. PubMed
- Schmidt, C., Abicht, A., Krampfl, K., Voss, W., Stucka, R., Mildner, G., Petrova, S., Schara, U., Mortier, W., Bufler, J., Huebner, A., and Lochmuller, H. Congenital myasthenic syndrome due to a novel missense mutation in the gene encoding choline acetyl
- Tamminga, C., Smith, R. C., Chang, S., Haraszti, J. S., and Davis, J. M. Depression associated with oral choline. Lancet 10-23-1976;2(7991):905. PubMed
- Wood, J. L. and Allison, R. G. Effects of consumption of choline and lecithin on neurological and cardiovascular systems. Fed.Proc. 1982;41(14):3015-3021.
- Growdon, J. H. and Gelenberg, A. J. Choline and lecithin administration to patients with tardive dyskinesia. Trans.Am.Neurol.Assoc. 1978;103:95-99.
- Smith, C. M., Swash, M., Exton-Smith, A. N., Phillips, M. J., Overstall, P. W., Piper, M. E., and Bailey, M. R. Choline therapy in Alzheimer's disease. Lancet 8-5-1978;2(8084):318. PubMed
- Morrison, L. M. and W. F. Gonzales. Choline in coronary atherosclerosis. Amer.Heart J. 1950;39:729.
- Christie, J. G. Blackburn 1. M. Glen A. I. M. Zeisel S. Shering A. & Yates C. M. Effects of choline and lecithin on CSF choline levels and on cognitive functioning in patients with presenile dementia of the Alzheimer type. Nutrition and the brain 1979;5
- Sidhu N, Davies S, Nadarajah A, et al. Oral choline supplementation for postoperative pain. Br J Anaesth 2013;111(2):249-55. PubMed
- Wozniak JR, Fuglestad AJ, Eckerle JK, et al. Choline supplementation in children with fetal alcohol spectrum disorders has high feasibility and tolerability. Nutr Res. 2013;33(11):897-904. PubMed
- Wozniak JR, Fuglestad AJ, Eckerle JK, et al. Choline supplementation in children with fetal alcohol disorders: a randomized, double-blind, placebo-controlled trial. Am J Clin Nutr. 2015;102(5): 1113-25.
- Ross RG, Hunter SK, McCarthy L, et al. Perinatal choline effects on neonatal pathophysiology related to later schizophrenia risk. Am J Psychiatry. 2013;170(3):290-8. PubMed
- Food and Nutrition Board, Institute of Medicine. Choline. Dietary Reference Intakes: Thiamin, Riboflavin, Niacin, Vitamin B-6, Vitamin B-12, Pantothenic Acid, Biotin, and Choline. Washington D.C.: National Academy Press; 1998:390-422.
Inositol 14 references
- Palatnik A, Frolov K, Fux M, Benjamin J. Double-blind, controlled, crossover trial of inositol versus fluvoxamine for the treatment of panic disorder. J Clin Psychopharmacol 2001;21:335-9.. PubMed
- Allan SJ, Kavanagh GM, Herd RM, Savin JA. The effect of inositol supplements on the psoriasis of patients taking lithium: a randomized, placebo-controlled trial. Br J Dermatol 2004;150:966-9. PubMed
- Machado-Vieira R, Viale CI, Kapczinski F. Mania associated with an energy drink: the possible role of caffeine, taurine, and inositol. Can J Psychiatry 2001;46:454-5. PubMed
- Kamenov Z, Kolarov G, Gateva A, Carlomagno G, Genazzani AD. Ovulation induction with myo-inositol alone and in combination with clomiphene citrate in polycystic ovarian syndrome patients with insulin resistance. Gynecol Endocrinol 2015;31(2):131-5. PubMed
- Matarrelli B, Vitacolonna E, D'Angelo M, et al. Effect of dietary myo-inositol supplementation in pregnancy on the incidence of maternal gestational diabetes mellitus and fetal outcomes: a randomized controlled trial. J Matern Fetal Neonatal Med 2013;26(1 PubMed
- Mukai T, Kishi T, Matsuda Y, Iwata N. A meta-analysis of inositol for depression and anxiety disorders. Hum Psychopharmacol 2014;29(1):55-63. PubMed
- Farren M, Daly N, McKeating A, Kinsley B, Turner MJ, Daly S. The Prevention of Gestational Diabetes Mellitus With Antenatal Oral Inositol Supplementation: A Randomized Controlled Trial. Diabetes Care. 2017;40(6):759-63. PubMed
- Zheng X, Liu Z, Zhang Y, et al. Relationship Between Myo-Inositol Supplementary and Gestational Diabetes Mellitus: A Meta-Analysis. Medicine (Baltimore). 2015;94(42):e1604. PubMed
- Crawford TJ, Crowther CA, Alsweiler J, Brown J. Antenatal dietary supplementation with myo-inositol in women during pregnancy for preventing gestational diabetes. Cochrane Database Syst Rev. 2015;(12):CD011507. PubMed
- Maurizi AR, Menduni M, Del Toro R, et al. A pilot study of D-chiro-inositol plus folic acid in overweight patients with type 1 diabetes. Acta Diabetol. 2017;54(4):361-65. PubMed
- Leppink EW, Redden SA, Grant JE. A double-blind, placebo-controlled study of inositol in trichotillomania. Int Clin Psychopharmacol. 2017;32(2):107-14. PubMed
- Lam S, Mandrekar SJ, Gesthalter Y. A Randomized Phase IIb Trial of myo-Inositol in Smokers with Bronchial Dysplasia. Cancer Prev Res (Phila). 2016;9(12):906-14.
- Wozniak J, Faraone SV, Chan J, et al. A randomized clinical trial of high eicosapentaenoic acid omega-3 fatty acids and inositol as monotherapy and in combination in the treatment of pediatric bipolar spectrum disorders: a pilot study. J Clin Psychiatry. PubMed
- Vitale SG, Corrado F, Caruso S, et al. Myo-inositol supplementation to prevent gestational diabetes in overweight non-obese women: bioelectrical impedance analysis, metabolic aspects, obstetric and neonatal outcomes - a randomized and open-label, placebo-
Magnesium 82 references
- Rodin SM, Johnson BF. Pharmacokinetic interactions with digoxin. Clin Pharmacokinet 1988;15:227-44.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Dahle LO, Berg G, Hammar M, et al. The effect of oral magnesium substitution on pregnancy-induced leg cramps. Am J Obstet Gynecol 1995;173:175-80. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Peikert A, Wilimzig C, Kohne-Volland R. Prophylaxis of migraine with oral magnesium: results from a prospective, multi-center, placebo-controlled and double-blind randomized study. Cephalalgia 1996;16:257-63. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Washington, DC: National Academy Press, 1999. Available at: http://books.nap.edu/books/0309063507/html/index.html.
- Birrer RB, Shallash AJ, Totten V. Hypermagnesemia-induced fatality following epsom salt gargles. J Emerg Med 2002;22:185-8. PubMed
- Ryan MP. Diuretics and potassium/magnesium depletion. Directions for treatment. Am J Med 1987;82:38-47.. PubMed
- Hollifield JW. Magnesium depletion, diuretics, and arrhythmias. Am J Med 1987;82:30-7.. PubMed
- Heidenreich O. Mode of action of conventional and potassium-sparing diuretics--aspects with relevance to Mg-sparing effects. Magnesium 1984;3:248-56..
- Pfaffenrath V, Wessely P, Meyer C, et al. Magnesium in the prophylaxis of migraine--a double-blind placebo-controlled study. Cephalalgia 1996;16:436-40.. PubMed
- Wang F, Van Den Eeden SK, Ackerson LM, et al. Oral magnesium oxide prophylaxis of frequent migrainous headache in children: a randomized, double-blind, placebo-controlled trial. Headache 2003;43:601-10.. PubMed
- Sompolinsky D, Samra Z. Influence of magnesium and manganese on some biological and physical properties of tetracycline. J Bacteriol 1972;110:468-76.. PubMed
- Jeyabalan A, Caritis SN. Pharmacologic inhibition of preterm labor. Clin Obstet Gynecol 2002;45:99-113. PubMed
- Mittendorf R, Dambrosia J, Pryde PG, et al. Association between the use of antenatal magnesium sulfate in preterm labor and adverse health outcomes in infants. Am J Obstet Gynecol 2002;186:1111-8.. PubMed
- Witlin AG, Sibai BM. Magnesium sulfate therapy in preeclampsia and eclampsia. Obstet Gynecol 1998;92:883-9.. DOI
- Crowther CA, Hiller JE, Doyle LW. Magnesium sulphate for preventing preterm birth in threatened preterm labour. Cochrane Database Syst Rev 2002;4:CD001060. . PubMed
- Davey MJ, Teubner D. A randomized controlled trial of magnesium sulfate, in addition to usual care, for rate control in atrial fibrillation. Ann Emerg Med 2005;45:347-53.. PubMed
- L'Hommedieu CS, Nicholas D, Armes DA, et al. Potentiation of magnesium sulfate--induced neuromuscular weakness by gentamicin, tobramycin, and amikacin. J Pediatr 1983;102:629-31..
- Dunn CJ, Goa KL. Risedronate: a review of its pharmacological properties and clinical use in resorptive bone disease. Drugs 2001;61:685-712..
- Kass L, Weekes J, Carpenter L. Effect of magnesium supplementation on blood pressure: a meta-analysis. Eur J Clin Nutr 2012;66:411-8. PubMed
- Koontz SL, Friedman SA, Schwartz ML. Symptomatic hypocalcemia after tocolytic therapy with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 2004;190(6):1773-6. PubMed
- Snyder SW, Cardwell MS. Neuromuscular blockade with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 1989;161(1):35-6. PubMed
- Waisman GD, Mayorga LM, Cámera MI, et al. Magnesium plus nifedipine: potentiation of hypotensive effect in preeclampsia? Am J Obstet Gynecol. 1988;159(2):308-9. PubMed
- Brown DD, Juhl RP. Decreased bioavailability of digoxin due to antacids and kaolin-pectin. N Engl J Med. 1976;295(19):1034-7. PubMed
- Allen MD, Greenblatt DJ, Harmatz JS, et al. Effect of magnesium--aluminum hydroxide and kaolin--pectin on absorption of digoxin from tablets and capsules. J Clin Pharmacol. 1981;21(1):26-30. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an in vitro study. Thromb Haemost. 1996;76(1):88-93. DOI
- Ravn HB, Kristensen SD, Vissinger H, et al. Magnesium inhibits human platelets. Blood Coagul Fibrinolysis. 1996;7(2):241-4. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an infusion study in healthy volunteers. Thromb Haemost. 1996;75(6):939-44. DOI
- Neuvonen PJ, Kivistö KT. The effects of magnesium hydroxide on the absorption and efficacy of two glibenclamide preparations. Br J Clin Pharmacol. 1991;32(2):215-20. PubMed
- Kivistö KT, Neuvonen PJ. Enhancement of absorption and effect of glipizide by magnesium hydroxide. Clin Pharmacol Ther. 1991;49(1):39-43. PubMed
- Neuvonen PJ, Kivistö KT. Enhancement of drug absorption by antacids. An unrecognised drug interaction. Clin Pharmacokinet. 1994;27(2):120-8. PubMed
- Shechter, M., Merz, C. N., Paul-Labrador, M., Meisel, S. R., Rude, R. K., Molloy, M. D., Dwyer, J. H., Shah, P. K., and Kaul, S. Beneficial antithrombotic effects of the association of pharmacological oral magnesium therapy with aspirin in coronary heart
- Ganzevoort, J. W., Hoogerwaard, E. M., and van der Post, J. A. [Hypocalcemic delirium due to magnesium sulphate therapy in a pregnant woman with pre-eclampsia]. Ned.Tijdschr.Geneeskd. 8-3-2002;146(31):1453-1456.
- Horner, S. M. Efficacy of intravenous magnesium in acute myocardial infarction in reducing arrhythmias and mortality. Meta-analysis of magnesium in acute myocardial infarction. Circulation 1992;86(3):774-779. PubMed
- Azria, E., Tsatsaris, V., Goffinet, F., Kayem, G., Mignon, A., and Cabrol, D. [Magnesium sulfate in obstetrics: current data]. J Gynecol.Obstet.Biol.Reprod.(Paris) 2004;33(6 Pt 1):510-517.
- Magee, L. A., Miremadi, S., Li, J., Cheng, C., Ensom, M. H., Carleton, B., Cote, A. M., and von Dadelszen, P. Therapy with both magnesium sulfate and nifedipine does not increase the risk of serious magnesium-related maternal side effects in women with p
- Henyan, N. N., Gillespie, E. L., White, C. M., Kluger, J., and Coleman, C. I. Impact of intravenous magnesium on post-cardiothoracic surgery atrial fibrillation and length of hospital stay: a meta-analysis. Ann.Thorac.Surg. 2005;80(6):2402-2406. PubMed
- Li, J., Zhang, Q., Zhang, M., and Egger, M. Intravenous magnesium for acute myocardial infarction. Cochrane.Database.Syst.Rev. 2007;(2):CD002755. PubMed
- Doyle, L. W., Crowther, C. A., Middleton, P., Marret, S., and Rouse, D. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane.Database.Syst.Rev. 2009;(1):CD004661. PubMed
- Han, S., Crowther, C. A., and Moore, V. Magnesium maintenance therapy for preventing preterm birth after threatened preterm labour. Cochrane.Database.Syst.Rev. 2010;(7):CD000940. PubMed
- Duley, L., Gulmezoglu, A. M., Henderson-Smart, D. J., and Chou, D. Magnesium sulphate and other anticonvulsants for women with pre-eclampsia. Cochrane.Database.Syst.Rev. 2010;(11):CD000025. PubMed
- Conde-Agudelo, A., Romero, R., and Kusanovic, J. P. Nifedipine in the management of preterm labor: a systematic review and metaanalysis. Am J Obstet.Gynecol. 2011;204(2):134-20. PubMed
- Wong, G. K., Boet, R., Poon, W. S., Chan, M. T., Gin, T., Ng, S. C., and Zee, B. C. Intravenous magnesium sulphate for aneurysmal subarachnoid hemorrhage: an updated systemic review and meta-analysis. Crit Care 2011;15(1):R52. PubMed
- Magee, L., Sawchuck, D., Synnes, A., and von, Dadelszen P. SOGC Clinical Practice Guideline. Magnesium sulphate for fetal neuroprotection. J Obstet.Gynaecol.Can. 2011;33(5):516-529.
- Doyle, L. W. Antenatal magnesium sulfate and neuroprotection. Curr Opin Pediatr 2012;24(2):154-159. PubMed
- McDonald, S. D., Lutsiv, O., Dzaja, N., and Duley, L. A systematic review of maternal and infant outcomes following magnesium sulfate for pre-eclampsia/eclampsia in real-world use. Int J Gynaecol.Obstet. 2012;118(2):90-96. PubMed
- Gordon, M., Naidoo, K., Akobeng, A. K., and Thomas, A. G. Osmotic and stimulant laxatives for the management of childhood constipation. Cochrane.Database.Syst.Rev. 2012;7:CD009118. PubMed
- Dodd, J. M., Crowther, C. A., and Middleton, P. Oral betamimetics for maintenance therapy after threatened preterm labour. Cochrane.Database.Syst.Rev. 2012;12:CD003927. PubMed
- Wu, X., Wang, C., Zhu, J., Zhang, C., Zhang, Y., and Gao, Y. Meta-analysis of randomized controlled trials on magnesium in addition to beta-blocker for prevention of postoperative atrial arrhythmias after coronary artery bypass grafting. BMC.Cardiovasc.D PubMed
- Thorp, J. M., Jr., Katz, V. L., Campbell, D., and Cefalo, R. C. Hypersensitivity to magnesium sulfate. Am.J.Obstet.Gynecol. 1989;161(4):889-890. PubMed
- Duley L and Gulmezoglu AM. Magnesium sulphate versus lytic cocktail for eclampsia. Cochrane Database of Systematic Reviews 2000;(3) PubMed
- Gibbins KJ, Browning KR, Lopes VV, Anderson BL, Rouse DJ. Evaluation of the clinical use of magnesium sulfate for cerebral palsy prevention. Obstet Gynecol 2013;121(2 Pt 1):235-40. PubMed
- Ji D. Oral magnesium sulfate causes perforation during bowel preparation for fiberoptic colonoscopy in patients with colorectal cancer. J Emerg Med 2012;43(4):716-7. PubMed
- Yagi T, Naito T, Mino Y, Umemura K, Kawakami J. Impact of concomitant antacid administration on gabapentin plasma exposure and oral bioavailability in healthy adult subjects. Drug Metab Pharmacokinet 2012;27(2):248-54. PubMed
- Yamasaki M, Funakoshi S, Matsuda S, Imazu T, Takeda Y, Murakami T, Maeda Y. Interaction of magnesium oxide with gastric acid secretion inhibitors in clinical pharmacotherapy. Eur J Clin Pharmacol 2014;70(8):921-4. PubMed
- Choi ES, Jeong WJ, Ahn SH, Oh AY, Jeon YT, Do SH. Magnesium sulfate accelerates the onset of low-dose rocuronium in patients undergoing laryngeal microsurgery. J Clin Anesth. 2017 Feb;36:102-106. PubMed
- Ikee R, Toyoyama T, Endo T, Tsunoda M, Hashimoto N. Impact of sevelamer hydrochloride on serum magnesium concentrations in hemodialysis patients. Magnes Res. 2016 Apr 1;29(4):184-90. PubMed
- Miller ES, Sakowicz A, Leger E. Lange E, Yee LM. The association between receipt of intrapartum magnesium and postpartum hemorrhage. Am J Obstet Gynecol 2018;218(1 Suppl):S165.
- Rodríguez-Rubio L, Solis Garcia Del Pozo J, Nava E, Jordán J. Interaction between magnesium sulfate and neuromuscular blockers during the perioperative period. A systematic review and meta-analysis. J Clin Anesth. 2016;34:524-34. PubMed
- Brown RS. Magnesium Sulfate: Another Cause of a Solute Diuresis. Am J Kidney Dis. 2017;69(4):550-551. PubMed
- Park H, Qin R, Smith TJ, et al. North Central Cancer Treatment Group N10C2 (Alliance): a double-blind placebo-controlled study of magnesium supplements to reduce menopausal hot flashes. Menopause. 2015;22(6):627-32. PubMed
- Sakanoue M, Sanada J, Kanekura T. Skin eruption elicited by magnesium oxide (Maglax). J Dermatol. 2016;43(2):221-2.
- Iwamuro M, Saito S, Yoshioka M, et al. A Magnesium Oxide Bezoar. Intern Med. 2018;57(21):3087-3091. PubMed
- Vilchez G, Dai J, Kumar K, Mundy D, Kontopoulos E, Sokol RJ. Racial/ethnic disparities in magnesium sulfate neuroprotection: a subgroup analysis of a multicenter randomized controlled trial. J Matern Fetal Neonatal Med. 2018;31(17):2304-2311. PubMed
- Drug Safety Communication: FDA Recommends Against Prolonged Use of Magnesium Sulfate to Stop Pre-term Labor Due to Bone Changes in Exposed Babies. U.S. Food and Drug Administration (FDA), May 30, 2013. https://www.fda.gov/downloads/Drugs/DrugSafety/UCM353
- Committee Opinion: Magnesium Sulfate Use in Obstetrics. The American College of Obstetricians and Gynecologists Committee on Obstetric Practice Society for Maternal-Fetal Medicine, Number 652, January 2016. https://www.acog.org/Clinical-Guidance-and-Publi
- Kashihara Y, Terao Y, Yoda K, et al. Effects of magnesium oxide on pharmacokinetics of L-dopa/carbidopa and assessment of pharmacodynamic changes by a model-based simulation. Eur J Clin Pharmacol. 2019;75(3):351-361. PubMed
- Shepherd E, Salam RA, Manhas D, et al. Antenatal magnesium sulphate and adverse neonatal outcomes: A systematic review and meta-analysis. PLoS Med. 2019;16(12):e1002988. PubMed
- Hong JY, Hong JY, Choi YS, et al. Antenatal magnesium sulfate treatment and risk of necrotizing enterocolitis in preterm infants born at less than 32 weeks of gestation. Sci Rep. 2020;10(1):12826. PubMed
- Schuh S, Sweeney J, Rumantir M, et al. Effect of nebulized magnesium vs placebo added to albuterol on hospitalization among children with refractory acute asthma treated in the emergency department: a randomized clinical trial. JAMA. 2020;324(20):2038-20 PubMed
- Almeida CED, Carvalho LR, Andrade CVC, Nascimento PD Jr, Barros GAM, Modolo NSP. Effects of magnesium sulphate on the onset time of rocuronium at different doses: a randomized clinical trial. Braz J Anesthesiol. 2021;71(5):482-8. PubMed
- Gochi Valdovinos A, Arriaga-Redondo M, Dejuan Bitriá E, Pérez Rodríguez I, Márquez Isidro E, Blanco Bravo D. Prenatal therapy with magnesium sulphate and intestinal obstruction due to meconium in preterm newborns. An Pediatr (Engl Ed). 2022 Feb;96(2):138- PubMed
- Iio K, Kondo E, Shibata E, et al. Long-term tocolysis with magnesium sulfate as a risk factor for low bone mass: a case series. J Med Cases. 2022 Feb;13(2):47-50. PubMed
- Eiraku K, Uozumi Y, Hieda M, Maruyama T, Nomura H. A senile case of heart failure associated with hypermagnesemia induced by magnesium-containing laxative agent. Geriatr Gerontol Int. 2022;22(10):897-899.
- Enayati A, Gin JH, Sajeev JK, et al. Efficacy of intravenous magnesium for the management of non-post operative atrial fibrillation with rapid ventricular response: A systematic review and meta-analysis. J Cardiovasc Electrophysiol 2023;34(5):1286-1295. PubMed
- Su YH, Luo DC, Pang Y. Effects of intraoperative Magnesium sulfate infusion on emergency agitation during general anesthesia in patients undergoing radical mastectomy: a randomized controlled study. BMC Anesthesiol 2023;23(1):326. PubMed
- Han J, Park HY, Shin HJ, Chung SH, Do SH. Effects of magnesium sulphate on neostigmine-induced recovery from moderate neuromuscular blockade with rocuronium: a randomized controlled trial. Magnes Res 2023;36(2):31-39. PubMed
- Lee AT, Cordova JC, Jamplis RP, Pomicter GR. Posterior Reversible Encephalopathy Syndrome and Eclampsia in the Setting of Magnesium Toxicity: A Case Report. A A Pract 2023;17(11):e01726. PubMed
- Darmawan D, Rengganis I, Rumende CM, et al. Effectiveness and Safety of Nebulized Magnesium as Last Line Treatment in Adults with Acute Asthma Attack: A Systematic Review and Meta-Analysis. Acta Med Indones 2024;56(1):3-12.
- Shepherd ES, Goldsmith S, Doyle LW, et al. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane Database Syst Rev 2024;5(5):CD004661. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Milk Thistle 69 references
- Ferenci P, Dragosics B, Dittrich H, et al. Randomized controlled trial of silymarin treatment in patients with cirrhosis of the liver. J Hepatol 1989;9:105-13. PubMed
- Anon. Milk thistle: Effects on liver disease and cirrhosis and clinical adverse effects. Summary, Evidence Report/Technology Assessment: Number 21, September 2000. Agency for Healthcare Research and Quality, Rockville, MD. Available at: http://www.ahrq.g
- Beckmann-Knopp S, Rietbrock S, Weyhenmeyer R, et al. Inhibitory effects of silibinin on cytochrome P-450 enzymes in human liver microsomes. Pharmacol Toxicol 2000;86:250-6. PubMed
- Venkataramanan R, Ramachandran V, Komoroski BJ, et al. Milk thistle, a herbal supplement, decreases the activity of CYP3A4 and uridine diphosphoglucuronosyl transferase in human hepatocyte cultures. Drug Metab Dispos 2000;28:1270-3. DOI
- Kim DH, Jin YH, Park JB, Kobashi K. Silymarin and its components are inhibitors of beta-glucuronidase. Biol Pharm Bull 1994;17:443-5. PubMed
- Pares A, Planas R, Torres M, et al. Effects of silymarin in alcoholic patients with cirrhosis of the liver: results of a controlled, double-blind, randomized and multicenter trial. J Hepatol 1998;28:615-21. PubMed
- Piscitelli SC, Formentini E, Burstein AH, et al. Effect of milk thistle on the pharmacokinetics of indinavir in healthy volunteers. Pharmacotherapy 2002;22:551-6. PubMed
- Boerth J, Strong KM. The clinical utility of milk thistle (Silybum marianum) in cirrhosis of the liver. J Herb Pharmacother 2002;2:11-7.
- Tanamly MD, Tadros F, Labeeb S, et al. Randomised double-blinded trial evaluating silymarin for chronic hepatitis C in an Egyptian village: study description and 12-month results. Dig Liver Dis 2004;36:752-9. PubMed
- Gurley BJ, Gardner SF, Hubbard MA, et al. In vivo assessment of botanical supplementation on human cytochrome P450 phenotypes: Citrus aurantium, Echinacea purpurea, milk thistle, and saw palmetto. Clin Pharmacol Ther 2004;76:428-40. .
- Huseini HF, Larijani B, Heshmat R, et al. The efficacy of Silybum marianum (L.) Gaertn. (silymarin) in the treatment of type II diabetes: a randomized, double-blind, placebo-controlled, clinical trial. Phytother Res 2006;20;1036-9.
- Deng JW, Shon JH, Shin HJ, et al. Effect of silymarin supplement on the pharmacokinetics of rosuvastatin. Pharm Res 2008;25:1807-14. PubMed
- Kim CS, Choi SJ, Park CY, et al. Effects of silybinin on the pharmacokinetics of tamoxifen and its active metabolite, 4-hydroxytamoxifen in rats. Anticancer Res 2010;30:79-85.
- Sridar C, Goosen TC, Kent UM, et al. Silybin inactivates cytochromes P450 3A4 and 2C9 and inhibits major hepatic glucuronosyltransferases. Drug Metab Dispos 2004;32:587-94. PubMed
- van Erp NP, Baker SD, Zhao M, et al. Effect of milk thistle (Silybum marianum) on the pharmacokinetics of irinotecan. Clin Cancer Res 2005;11:7800-6.
- Budzinski JW, Trudeau VL, Drouin CE, et al. Modulation of human cytochrome P450 3A4 (CYP3A4) and P-glycoprotein (P-gp) in Caco-2 cell monolayers by selected commercial-source milk thistle and goldenseal products. Can J Physiol Pharmacol 2007;85:966-78.
- Doehmer J, Weiss G, McGregor GP, Appel K. Assessment of a dry extract from milk thistle (Silybum marianum) for interference with human liver cytochrome-P450 activities. Toxicol In Vitro 2011;25:21-7. PubMed
- Jiao Z, Shi XJ, Li ZD, et al. Population pharmacokinetics of sirolimus in de novo Chinese adult renal transplant patients. Br.J.Clin.Pharmacol. 2009;68(1):47-60.
- Gurley, B. J., Barone, G. W., Williams, D. K., Carrier, J., Breen, P., Yates, C. R., Song, P. F., Hubbard, M. A., Tong, Y., and Cheboyina, S. Effect of milk thistle (Silybum marianum) and black cohosh (Cimicifuga racemosa) supplementation on digoxin phar
- Allain, H., Schuck, S., Lebreton, S., Strenge-Hesse, A., Braun, W., Gandon, J. M., and Brissot, P. Aminotransferase levels and silymarin in de novo tacrine-treated patients with Alzheimer's disease. Dement.Geriatr.Cogn Disord. 1999;10(3):181-185. PubMed
- Angulo, P., Patel, T., Jorgensen, R. A., Therneau, T. M., and Lindor, K. D. Silymarin in the treatment of patients with primary biliary cirrhosis with a suboptimal response to ursodeoxycholic acid. Hepatology 2000;32(5):897-900. PubMed
- Bean, P. The use of alternative medicine in the treatment of hepatitis C. Am.Clin.Lab 2002;21(4):19-21.
- Hussain, S. A. Silymarin as an adjunct to glibenclamide therapy improves long-term and postprandial glycemic control and body mass index in type 2 diabetes. J.Med.Food 2007;10(3):543-547. PubMed
- El-Kamary, S. S., Shardell, M. D., Abdel-Hamid, M., Ismail, S., El-Ateek, M., Metwally, M., Mikhail, N., Hashem, M., Mousa, A., Aboul-Fotouh, A., El-Kassas, M., Esmat, G., and Strickland, G. T. A randomized controlled trial to assess the safety and effic
- Gharagozloo, M., Moayedi, B., Zakerinia, M., Hamidi, M., Karimi, M., Maracy, M., and Amirghofran, Z. Combined therapy of silymarin and desferrioxamine in patients with beta-thalassemia major: a randomized double-blind clinical trial. Fundam.Clin.Pharmaco
- Ladas, E. J., Kroll, D. J., Oberlies, N. H., Cheng, B., Ndao, D. H., Rheingold, S. R., and Kelly, K. M. A randomized, controlled, double-blind, pilot study of milk thistle for the treatment of hepatotoxicity in childhood acute lymphoblastic leukemia (ALL PubMed
- Sayyah, M., Boostani, H., Pakseresht, S., and Malayeri, A. Comparison of Silybum marianum (L.) Gaertn. with fluoxetine in the treatment of Obsessive-Compulsive Disorder. Prog.Neuropsychopharmacol.Biol.Psychiatry 3-17-2010;34(2):362-365. PubMed
- Flaig, T. W., Glode, M., Gustafson, D., van, Bokhoven A., Tao, Y., Wilson, S., Su, L. J., Li, Y., Harrison, G., Agarwal, R., Crawford, E. D., Lucia, M. S., and Pollak, M. A study of high-dose oral silybin-phytosome followed by prostatectomy in patients w
- Ramirez-Santos, A., Perez-Bustillo, A., Gonzalez-Sixto, B., Suarez-Amor, O., and Rodriguez-Prieto, M. A. [Acute generalized exanthematous pustulosis due to milk thistle (Silybum marianum) tea]. Actas Dermosifiliogr. 2011;102(9):744-745. DOI
- Loguercio C, Andreone P, Brisc C, et al. Silybin combined with phosphatidylcholine and vitamin E in patients with nonalcoholic fatty liver disease: a randomized controlled trial. Free Radic Biol Med 2012;52(9):1658-65. PubMed
- Yakoot, M. and Salem, A. Spirulina platensis versus silymarin in the treatment of chronic hepatitis C virus infection. A pilot randomized, comparative clinical trial. BMC.Gastroenterol. 2012;12:32. PubMed
- Fallahzadeh, M. K., Dormanesh, B., Sagheb, M. M., Roozbeh, J., Vessal, G., Pakfetrat, M., Daneshbod, Y., Kamali-Sarvestani, E., and Lankarani, K. B. Effect of addition of silymarin to renin-angiotensin system inhibitors on proteinuria in type 2 diabetic
- Fried, M. W., Navarro, V. J., Afdhal, N., Belle, S. H., Wahed, A. S., Hawke, R. L., Doo, E., Meyers, C. M., and Reddy, K. R. Effect of silymarin (milk thistle) on liver disease in patients with chronic hepatitis C unsuccessfully treated with interferon t
- Fallah Huseini, H., Larijani, B., Fakhrzadeh, H., Rajabi Pour, B., Akhondzadeh, S., Toliat, T., and Heshmat, R. The clinical trial of Silybum Marianum seed extract (Silymarin) on type II diabetic patients with hyperlipidemia. Iran J.Diabetes Lipid Disord
- Mironets VI, Krasovskaia EA, and Polishchuk II. [A case of urticaria during Carsil treatment]. Vrach Delo 1990;7:86-87.
- Velussi M, Cernigoi AM, Viezzoli L, and et al. Silymarin reduces hyperinsulinemia, malondialdehyde levels, and daily insulin need in cirrhotic diabetic patients. Curr Ther Res 1993;53(5):533-545. DOI
- Marcelli R, Bizzoni P, Conte D, and et al. Randomized controlled study of the efficacy and tolerability of a short course of IdB 1016 in the treatment of chronic persistent hepatitis. Eur Bull Drug Res 1992;1(3):131-135.
- Vailati A, Aristia L, Sozze E, and et al. Randomized open study of the dose-effect relationship of a short course of IdB 1016 in patients with viral or alcoholic hepatitis. Fitoterapia 1993;64(3):219-228.
- Marena C and Lampertico M. Preliminary clinical development of silipide: a new complex of silybin in toxic liver disorders. Planta Med 1991;57(2):A124-A125. DOI
- Grungreiff K, Albrecht M, and Strenge-Hesse A. Benefit of medicinal liver therapy in general practice. Med Welt 1995;46:222-227.
- Frerick F, Kuhn U, and Strenge-Hesse A. Silymarin--ein Phytopharmakon zur Behandlung toxischen Leberschaden: Anwendungsbeobachtung bei 2169 Patienten. Kassenarzt 1990;33:36-41.
- Schuppan D, Strosser W, Burkard G, and et al. Influence of Legalon(TM) 140 on the metabolism of collagen in patients with chronic liver disease--Review by measurement of PIIINP-values. Zeitschrift fur Allgemeinmedizin 1998;74:577-584.
- Studlar M. Die Behandlung chronischer Leberkrankungen mit Silymarin und B-Vitaminen. Therapiewoche 1985;35:3375-3378.
- Anon. Adverse reaction: milk thistle-associated toxicity. Nurse Drug Alert 1999;23(7):51.
- Gufford BT, Chen G, Vergara AG, et al. Milk Thistle Constituents Inhibit Raloxifene Intestinal Glucuronidation: A Potential Clinically Relevant Natural Product-Drug Interaction. Drug Metab Dispos. 2015;43(9):1353-9. PubMed
- El-Shitany NA, Hegazy S, El-Desoky K. Evidences for antiosteoporotic and selective estrogen receptor modulator activity of silymarin compared with ethinylestradiol in ovariectomized rats. Phytomedicine. 2010;17(2):116-25. PubMed
- Seidlová-Wuttke D, Becker T, Christoffel V, Jarry H, Wuttke W. Silymarin is a selective estrogen receptor beta (ERbeta) agonist and has estrogenic effects in the metaphysis of the femur but no or antiestrogenic effects in the uterus of ovariectomized (ovx
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Derosa G, Romano D, D'Angelo A, Maffioli P. Berberis aristata/Silybum marianum fixed combination (Berberol(®)) effects on lipid profile in dyslipidemic patients intolerant to statins at high dosages: a randomized, placebo-controlled, clinical trial. Phyto PubMed
- Luangchosiri C, Thakkinstian A, Chitphuk S, Stitchantrakul W, Petraksa S, Sobhonslidsuk A. A double-blinded randomized controlled trial of silymarin for the prevention of antituberculosis drug-induced liver injury. BMC Complement Altern Med. 2015;15:334. PubMed
- Kawaguchi-Suzuki M, Frye RF, Zhu HJ, et al. The effects of milk thistle (Silybum marianum) on human cytochrome P450 activity. Drug Metab Dispos. 2014;42(10):1611-6. PubMed
- Rastegarpanah M, Malekzadeh R, Vahedi H, et al. A randomized, double blinded, placebo-controlled clinical trial of silymarin in ulcerative colitis. Chin J Integr Med. 2015;21(12):902-6. PubMed
- Di Pierro F, Bellone I, Rapacioli G, Putignano P. Clinical role of a fixed combination of standardized Berberis aristata and Silybum marianum extracts in diabetic and hypercholesterolemic patients intolerant to statins. Diabetes Metab Syndr Obes. 2015;8:8 PubMed
- Di Pierro F, Villanova N, Agostini F, Marzocchi R, Soverini V, Marchesini G. Pilot study on the additive effects of berberine and oral type 2 diabetes agents for patients with suboptimal glycemic control. Diabetes Metab Syndr Obes. 2012;5:213-7. PubMed
- Guarino G, Strollo F, Carbone L, et al. Bioimpedance analysis, metabolic effects and safety of the association Berberis aristata/Bilybum marianum: a 52-week double-blind, placebo-controlled study in obese patients with type 2 diabetes. J Biol Regul Homeos
- Ebrahimpour-Koujan S, Gargari BP, Mobasseri M, Valizadeh H, Asghari-Jafarabadi M. Lower glycemic indices and lipid profile among type 2 diabetes mellitus patients who received novel dose of Silybum marianum (L.) Gaertn. (silymarin) extract supplement: A T
- Lash DB, Ward S. CYP2C9-mediated warfarin and milk thistle interaction. J Clin Pharm Ther. 2019. PubMed
- Malekshah RE, Khaleghian A. Influence of Silybum marianum on morphine addicted rats, biochemical parameters and molecular simulation studies on µ-opioid receptor. Drug Res (Stuttg). 2019;69(11):630-638. PubMed
- Soleymani S, Ayati MH, Mansourzadeh MJ, Namazi N, Zargaran A. The effects of Silymarin on the features of cardiometabolic syndrome in adults: A systematic review and meta-analysis. Phytother Res. 2022 Jan 11. doi: 10.1002/ptr.7364. PubMed
- Gamissans M, Expósito-Serrano V, López-Llunell C, Valdivieso L, Garbayo-Salmons P. Bullous pemphigoid triggered by Silybum marianum: an unexpected side effect of an herbal remedy. Int J Dermatol. 2021 Aug 7. doi: 10.1111/ijd.15822. PubMed
- Aboras SI, Korany MA, El-Yazbi AF, Ragab MAA, Abdine HH. In-depth investigation of the Silymarin effect on the pharmacokinetic parameters of sofosbuvir, GS-331007 and ledipasvir in rat plasma using LC-MS. Biomed Chromatogr 2022;36(9):e5427. PubMed
- Wattanakrai P, Nimmannitya K. A Randomized, Double-Blind, Split-Face Study of Topical Silymarin vs 2% Hydroquinone Cream in Melasmas. J Drugs Dermatol 2022;21(12):1304-1310. PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
- Zhang W, Zhang Y, Wen C, Jiang X, Wang L. In vitro Assessment of the Effects of Silybin on CYP2B6-mediated Metabolism. Planta Med 2023. PubMed
- Bechtold BJ, Lynch KD, Oyanna VO, et al. Rifampin- and Silymarin-Mediated Pharmacokinetic Interactions of Exogenous and Endogenous Substrates in a Transgenic OATP1B Mouse Model. Mol Pharm 2024;21(5):2284-2297. PubMed
- Mohammadi S, Asbaghi O, Afrisham R, et al. Impacts of Supplementation with Silymarin on Cardiovascular Risk Factors: A Systematic Review and Dose-Response Meta-Analysis. Antioxidants (Basel) 2024;13(4):390. PubMed
- Rustamzadeh A, Sadigh N, Vahabi Z, et al. Effects silymarin and rosuvastatin on amyloid-carriers level in dyslipidemic Alzheimer's patients: A double-blind placebo-controlled randomized clinical trial. IBRO Neurosci Rep 2024;17:108-121. PubMed
- Fatemi Shandiz A, Karimi G, Dayyani M, Hosseini S, Elyasi S. Evaluation of oral silymarin formulation efficacy in prevention of doxorubicin induced hepatotoxicity in patients with non-metastatic breast cancer. J Oncol Pharm Pract 2024. PubMed
- Duan X, Bai W, Hu J, et al. Inhibitory effect of flavonoids on multidrug and toxin extrusion protein 1 function: Implications for food/herb-drug interaction and drug-induced kidney injury. J Appl Toxicol 2024;44(9):1388-1402. PubMed
Dandelion 27 references
- Maliakal PP, Wanwimolruk S. Effect of herbal teas on hepatic drug metabolizing enzymes in rats. J Pharm Pharmacol 2001;53:1323-9. PubMed
- Williams CA, Goldstone F, Greenham J. Flavonoids, cinnamic acids and coumarins from the different tissues and medicinal preparations of Taraxacum officinale. Phytochemistry 1996;42:121-7. PubMed
- Hussain Z, Waheed A, Qureshi RA, et al. The effect of medicinal plants of Islamabad and Murree region of Pakistan on insulin secretion from INS-1 cells. Phytother Res 2004;18:73-7. PubMed
- Racz-Kotilla E, Racz G, Solomon A. The action of Taraxacum officinale extracts on the body weight and diuresis of laboratory animals. Planta Med 1974;26:212-7. PubMed
- Zhu M, Wong PY, Li RC. Effects of taraxacum mongolicum on the bioavailability and disposition of ciprofloxacin in rats. J Pharm Sci 1999;88:632-4. PubMed
- Jovanovic M, Mimica-Dukic N, Poljacki M, Boza P. Erythema multiforme due to contact with weeds: a recurrence after patch testing. Contact Dermatitis 2003;48:17-25. PubMed
- Chivato T, Juan F, Montoro A, Laguna R. Anaphylaxis induced by ingestion of a pollen compound. J Investig Allergol Clin Immunol 1996;6:208-9.
- Cohen SH, Yunginger JW, Rosenberg N, Fink JN. Acute allergic reaction after composite pollen ingestion. J Allergy Clin Immunol 1979;64:270-4. PubMed
- Lovell CR, Rowan M. Dandelion dermatitis. Contact Dermatitis 1991;25:185-8. PubMed
- Agarwal SC, Crook JR, Pepper CB. Herbal remedies -- how safe are they? A case report of polymorphic ventricular tachycardia/ventricular fibrillation induced by herbal medication used for obesity. Int J Cardiol 2006;106:260-1. PubMed
- Martín-Muñoz MF, Bartolome B, Caminoa M, et al. Bee pollen: a dangerous food for allergic children. Identification of responsible allergens. Allergol Immunopathol (Madr) 2010;38:263-5. PubMed
- Neef H, Cilli F, Declerck PJ, et al. Platelet anti-aggregating activity of Taraxacum officinale Weber. Phytotherapy Research 1996;10:s138-s140.
- Cuzzolin L, Zaffani S, and Benoni G. Safety implications regarding use of phytomedicines. Eur.J Clin Pharmacol. 2006;62:37-42. PubMed
- Posadzki, P., Watson, L. K., and Ernst, E. Adverse effects of herbal medicines: an overview of systematic reviews. Clin Med 2013;13(1):7-12. PubMed
- Wakelin, S. H., Marren, P., Young, E., and Shaw, S. Compositae sensitivity and chronic hand dermatitis in a seven-year-old boy. Br J Dermatol 1997;137(2):289-291. PubMed
- Ingber, A. Seasonal allergic contact dermatitis from Taraxacum officinale (dandelion) in an Israeli florist. Contact Dermatitis 2000;43(1):49.
- Rodriguez, B., Rodriguez, A., de Barrio, M., Tornero, P., and Baeza, M. L. Asthma induced by canary food mix. Allergy Asthma Proc. 2003;24(4):265-268.
- Syhaieva, I. A. [Efficiency of specific immunotherapy in treatment of patients with seasonal allergic rhinitis]. Lik.Sprava. 2006;(1-2):51-53.
- Catania, M. A., Oteri, A., Caiello, P., Russo, A., Salvo, F., Giustini, E. S., Caputi, A. P., and Polimeni, G. Hemorrhagic cystitis induced by an herbal mixture. South.Med.J. 2010;103(1):90-92. PubMed
- Goksu, E., Eken, C., Karadeniz, O., and Kucukyilmaz, O. First report of hypoglycemia secondary to dandelion (Taraxacum officinale) ingestion. Am J Emerg.Med 2010;28(1):111-112. PubMed
- Fernandez-Gonzalez, D., Gonzalez-Parrado, Z., Vega-Maray, A. M., Valencia-Barrera, R. M., Camazon-Izquierdo, B., De, Nuntiis P., and Mandrioli, P. Platanus pollen allergen, Pla a 1: quantification in the atmosphere and influence on a sensitizing populati
- Liang, K. L., Su, M. C., Shiao, J. Y., Wu, S. H., Li, Y. H., and Jiang, R. S. Role of pollen allergy in Taiwanese patients with allergic rhinitis. J Formos.Med Assoc. 2010;109(12):879-885. PubMed
- Yang, Y., Zhao, Y., Wang, C. S., Wang, X. D., and Zhang, L. [Prevalence of sensitization to aeroallergens in 10 030 patients with allergic rhinitis]. Zhonghua Er.Bi Yan.Hou Tou.Jing.Wai Ke Za Zhi 2011;46(11):914-920.
- Davies, M. G. and Kersey, P. J. Contact allergy to yarrow and dandelion. Contact Dermatitis 1986;14(4):256-257. PubMed
- Collins JM and Miller DR. Dandelion green bezoar following antrectomy and vagotomy - case report. J Kansas Med Soc 1966;67(6):303-304.
- Moriarty B, Pinney JH, Owen-Casey MP, Rustin MH, Deroide F, Laing C, Davenport A. Digital necrosis from dandelion tea. Br J Dermatol. 2013 Jul;169(1):227-30. PubMed
- Onal S, Timur S, Okutucu B, Zihnioglu F. Inhibition of alphaglucosidase by aqueous extracts of some potent antidiabetic medicinal herbs. Prep Biochem Biotechnol 2005;35:29-36.
Radish 5 references
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Damiani E, Aloia AM, Priore MG, Nardulli S, Ferrannini A. Generalized urticaria after ingestion of Raphanus sativus. Ann Allergy Asthma Immunol. 2011 Feb;106(2):168. PubMed
- Evans M, Paterson E, Barnes DM. An open label pilot study to evaluate the efficacy of Spanish black radish on the induction of phase I and phase II enzymes in healthy male subjects. BMC Complement Altern Med. 2014 Dec 9;14:475. PubMed
- Banihani SA. Radish (Raphanus sativus) and diabetes. Nutrients. 2017;9(9). pii: E1014. PubMed
- Shukla S, Chatterji S, Mehta S, Rai PK, Singh RK, Yadav DK, Watal G. Antidiabetic effect of Raphanus sativus root juice. Pharm Biol. 2011 Jan;49(1):32-7.
European Barberry 15 references
- Chan E. Displacement of bilirubin from albumin by berberine. Biol Neonate 1993;63:201-8. PubMed
- Wu X, Li Q, Xin H, Yu A, Zhong M. Effects of berberine on the blood concentration of cyclosporin A in renal transplanted recipients: clinical and pharmacokinetic study. Eur J Clin Pharmacol 2005;61:567-72. PubMed
- Shamsa F, Ahmadiani A, Khosrokhavar R. Antihistaminic and anticholinergic activity of barberry fruit (Berberis vulgaris) in the guinea-pig ileum. J Ethnopharmacol 1999;64:161-6. PubMed
- Fatehi M, Saleh TM, Fatehi-Hassanabad Z, et al. A pharmacological study on Berberis vulgaris fruit extract. J Ethnopharmacol 2005;102:46-52. PubMed
- Kostalova, D., Bukovsky, M., Koscova, H., and Kardosova, A. [Anticomplement activity of Mahonia aquifolium bisbenzylisoquinoline alkaloids and berberine extract]. Ceska.Slov.Farm 2001;50(6):286-289.
- Fatehi-Hassanabad, Z., Jafarzadeh, M., Tarhini, A., and Fatehi, M. The antihypertensive and vasodilator effects of aqueous extract from Berberis vulgaris fruit on hypertensive rats. Phytother Res 2005;19(3):222-225.
- Singh, J. and Kakkar, P. Antihyperglycemic and antioxidant effect of Berberis aristata root extract and its role in regulating carbohydrate metabolism in diabetic rats. J Ethnopharmacol. 5-4-2009;123(1):22-26. PubMed
- Shanbhag, S. M., Kulkarni, H. J., and Gaitonde, B. B. Pharmacological actions of berberine on the central nervous system. Jpn.J Pharmacol 1970;20(4):482-487. PubMed
- Wu, J. F. and Liu, T. P. [Effects of berberine on platelet aggregation and plasma levels of TXB2 and 6-keto-PGF1 alpha in rats with reversible middle cerebral artery occlusion]. Yao Xue.Xue.Bao. 1995;30(2):98-102.
- Xuan, B., Wang, W., and Li, D. X. Inhibitory effect of tetrahydroberberine on platelet aggregation and thrombosis. Zhongguo Yao Li Xue.Bao. 1994;15(2):133-135.
- Gao, C. R., Zhang, J. Q., and Huang, Q. L. [Experimental study on berberin raised insulin sensitivity in insulin resistance rat models]. Zhongguo Zhong.Xi.Yi.Jie.He.Za Zhi. 1997;17(3):162-164. DOI
- Sabir M and Bhide NK. Study of some pharmacological actions of berberine. Ind J Physiol & Pharmac 1971;15(3):111-132.
- Tripathi YB and Shukla SD. Berberis artistata inhibits PAF induced aggregation of rabbit platelets. Phytotherapy Research 1996;10:628-630.
- Lazavi F, Mirmiran P, Sohrab G, Nikpayam O, Angoorani P, Hedayati M. The barberry juice effects on metabolic factors and oxidative stress in patients with type 2 diabetes: A randomized clinical trial. Complement Ther Clin Pract. 2018;31:170-174. PubMed
- Philips CA, Theruvath AH, Ravindran R. Toxic hepatitis-associated aplastic anaemia after dual homeopathic remedies and Gymnema sylvestre use. BMJ Case Rep 2022;15(3):e247867. PubMed
Beet 14 references
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Clifford T, Berntzen B, Davison GW, et al. Effects of beetroot juice on recovery of muscle function and performance between bouts of repeated sprint exercise. Nutrients 2016;8. pii: E506. PubMed
- Siervo M, Lara J, Ogbonmwan I, Mathers JC. Inorganic nitrate and beetroot juice supplementation reduces blood pressure in adults: a systematic review and meta-analysis. J Nutr 2013;143:818-26. PubMed
- Clifford T, Howatson G, West DJ, Stevenson EJ. Beetroot juice is more beneficial than sodium nitrate for attenuating muscle pain after strenuous eccentric-bias exercise. Appl Physiol Nutr Metab. 2017;42(11):1185-1191. PubMed
- Clifford T, Bell O, West DJ, Howatson G, Stevenson EJ. The effects of beetroot juice supplementation on indices of muscle damage following eccentric exercise. Eur J Appl Physiol. 2016;116(2):353-62. PubMed
- Wylie LJ, Kelly J, Bailey SJ, et al. Beetroot juice and exercise: pharmacodynamic and dose-response relationships. J Appl Physiol (1985). 2013;115(3):325-36. PubMed
- Garnacho-Castaño MV, Palau-Salvà G, Cuenca E, et al. Effects of a single dose of beetroot juice on cycling time trial performance at ventilatory thresholds intensity in male triathletes. J Int Soc Sports Nutr. 2018;15(1):49. PubMed
- Rasica L, Porcelli S, Marzorati M, et al. Ergogenic effects of beetroot juice supplementation during severe-intensity exercise in obese adolescents. Am J Physiol Regul Integr Comp Physiol. 2018;315(3):R453-R460. PubMed
- Henrohn D, Björkstrand K, Lundberg JO, et al. Effects of oral supplementation with nitrate-rich beetroot juice in patients with pulmonary arterial hypertension-results from BEET-PAH, an exploratory randomized, double-blind, placebo-controlled, crosso
- Serra-Payá N, Garnacho-Castaño MV, Sánchez-Nuño S, et al. The relationship between resistance exercise performance and ventilatory efficiency after beetroot juice intake in well-trained athletes. Nutrients 2021;13(4):1094. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Hemmatinafar M, Zaremoayedi L, Koushkie Jahromi M, et al. Effect of Beetroot Juice Supplementation on Muscle Soreness and Performance Recovery after Exercise-Induced Muscle Damage in Female Volleyball Players. Nutrients 2023;15(17):3763. PubMed
- Lim SH, Bae S, Lee HS, Han HK, Choi CI. Effect of Betanin, the Major Pigment of Red Beetroot (Beta vulgaris L.), on the Activity of Recombinant Human Cytochrome P450 Enzymes. Pharmaceuticals (Basel) 2023;16(9):1224. PubMed
- Oscherwitz M, Tamayo RM, Heudebert A, Centor R. A Case of Pseudo-Hematochezia from Beet Supplement Ingestion. Am J Med 2023;136(9):e177-e178. PubMed
Greater Celandine 25 references
- Benninger J, Schneider HT, Schuppan D, et al. Acute hepatitis induced by greater celandine (Chelidonium majus). Gastroenterology 1999;117:1234-7. PubMed
- Holtmann G, Madisch A, Juergen H, et al. A double-blind, randomized, placebo-controlled trial on the effects of an herbal preparation in patients with functional dyspepsia [Abstract]. Ann Mtg Digestive Disease Week 1999 May.
- Madisch A, Holtmann G, Mayr G, et al. Treatment of functional dyspepsia with a herbal preparation. A double-blind, randomized, placebo-controlled, multicenter trial. Digestion 2004;69:45-52. PubMed
- Melzer J, Rosch W, Reichling J, et al. Meta-analysis: phytotherapy of functional dyspepsia with the herbal drug preparation STW 5 (Iberogast). Aliment Pharmacol Ther 2004;20:1279-87. PubMed
- Ernst E, Schmidt K. Ukrain - a new cancer cure? A systematic review of randomised clinical trials. BMC Cancer 2005;5:69. PubMed
- Stickel F, Poschl G, Seitz HK, et al. Acute hepatitis induced by Greater Celandine (Chelidonium majus). Scand J Gastroenterol 2003;38:565-8.
- Etxenagusia MA, Anda M, Gonzalez-Mahave I, et al. Contact dermatitis from Chelidonium majus (greater celandine). Contact Dermatitis 2000;43:47.
- Panzer A, Joubert AM, Bianchi PC, Seegers JC. The antimitotic effects of Ukrain, a Chelidonium majus alkaloid derivative, are reversible in vitro. Cancer Lett 2000;150:85-92. PubMed
- Moro PA, Cassetti F, Giugliano G, et al. Hepatitis from greater celandine (Chelidonium majus L.): Review of literature and report of a new case. J Ethnopharmacol 2009;124:328-32. PubMed
- Stickel, F., Seitz, H. K., Hahn, E. G., and Schuppan, D. [Liver toxicity of drugs of plant origin]. Z.Gastroenterol. 2001;39(3):225-227.
- Gansauge, F., Ramadani, M., Pressmar, J., Gansauge, S., Muehling, B., Stecker, K., Cammerer, G., Leder, G., and Beger, H. G. NSC-631570 (Ukrain) in the palliative treatment of pancreatic cancer. Results of a phase II trial. Langenbecks Arch.Surg. 2002;38 PubMed
- Nowicky, J. W., Manolakis, G., Meijer, D., Vatanasapt, V., and Brzosko, W. J. Ukrain both as an anti cancer and immunoregulatory agent. Drugs Exp.Clin Res 1992;18 Suppl:51-54.
- Staniszewski, A., Slesak, B., Kolodziej, J., Harlozinska-Szmyrka, A., and Nowicky, J. W. Lymphocyte subsets in patients with lung cancer treated with thiophosphoric acid alkaloid derivatives from Chelidonium majus L. (Ukrain). Drugs Exp.Clin Res 1992;18
- Nowicky, J. W., Staniszewski, A., Zbroja-Sontag, W., Slesak, B., Nowicky, W., and Hiesmayr, W. Evaluation of thiophosphoric acid alkaloid derivatives from Chelidonium majus L. ("Ukrain") as an immunostimulant in patients with various carcinomas. Drugs Ex
- Gansauge, F., Ramadani, M., Schwarz, M., Beger, H. G., Lotspeich, E., and Poch, B. The clinical efficacy of adjuvant systemic chemotherapy with gemcitabine and NSC-631570 in advanced pancreatic cancer. Hepatogastroenterology 2007;54(75):917-920.
- Hardeman, E., Van, Overbeke L., Ilegems, S., and Ferrante, M. Acute hepatitis induced by greater celandine (Chelidonium majus). Acta Gastroenterol.Belg. 2008;71(2):281-282.
- Gilca, M., Gaman, L., Panait, E., Stoian, I., and Atanasiu, V. Chelidonium majus--an integrative review: traditional knowledge versus modern findings. Forsch.Komplementmed. 2010;17(5):241-248. PubMed
- Teschke, R., Glass, X., and Schulze, J. Herbal hepatotoxicity by Greater Celandine (Chelidonium majus): causality assessment of 22 spontaneous reports. Regul.Toxicol.Pharmacol. 2011;61(3):282-291. PubMed
- Teschke, R., Glass, X., Schulze, J., and Eickhoff, A. Suspected Greater Celandine hepatotoxicity: liver-specific causality evaluation of published case reports from Europe. Eur.J Gastroenterol.Hepatol. 2012;24(3):270-280. PubMed
- Pinto, Garcia, V, Vicente, P. R., Barez, A., Soto, I., Candas, M. A., and Coma, A. [Hemolytic anemia induced by Chelidonium majus. Clinical case]. Sangre (Barc.) 1990;35(5):401-403.
- Teschke, R., Frenzel, C., Glass, X., Schulze, J., and Eickhoff, A. Greater Celandine hepatotoxicity: a clinical review. Ann.Hepatol. 2012;11(6):838-848. DOI
- Xian, M. S., Hayashi, K., Lu, J. P., and Awai, M. Efficacy of traditional Chinese herbs on squamous cell carcinoma of the esophagus: histopathologic analysis of 240 cases. Acta Med.Okayama 1989;43(6):345-351.
- Pantano F, Mannocchi G, Marinelli E, Gentili S, Graziano S, Busardò FP, di Luca NM. Hepatotoxicity induced by greater celandine (Chelidonium majus L.): a review of the literature. Eur Rev Med Pharmacol Sci. 2017 Mar;21(1 Suppl):46-52.
- Baek SC, Ryu HW, Kang MG, et al. Selective inhibition of monoamine oxidase A by chelerythrine, an isoquinoline alkaloid. Bioorg Med Chem Lett. 2018;28(14):2403-2407. PubMed
- Liu Y, Cui T, Peng Y, Ji M, Zheng J. Mechanism-based inactivation of cytochrome P450 2D6 by chelidonine. J Biochem Mol Toxicol. 2019;33(2):e22251. PubMed
Green Tea 219 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Harder S, Fuhr U, Staib AH, Wolff T. Ciprofloxacin-caffeine: a drug interaction established using in vivo and in vitro investigations. Am J Med 1989;87:89S-91S. PubMed
- Carbo M, Segura J, De la Torre R, et al. Effect of quinolones on caffeine disposition. Clin Pharmacol Ther 1989;45:234-40. PubMed
- Healy DP, Polk RE, Kanawati L, et al. Interaction between oral ciprofloxacin and caffeine in normal volunteers. Antimicrob Agents Chemother 1989;33:474-8. PubMed
- Mester R, Toren P, Mizrachi I, et al. Caffeine withdrawal increases lithium blood levels. Biol Psychiatry 1995;37:348-50. PubMed
- Jefferson JW. Lithium tremor and caffeine intake: two cases of drinking less and shaking more. J Clin Psychiatry 1988;49:72-3.
- Mitscher LA, Mitscher LA, Jung M, Shankel D, et al. Chemoprotection: a review of the potential therapeutic antioxidant properties of green tea (Camellia sinensis) and certain of its constituents. Med Res Rev 1997;17:327-65.
- Joeres R, Klinker H, Heusler H, et al. Influence of mexiletine on caffeine elimination. Pharmacol Ther 1987;33:163-9. PubMed
- Vahedi K, Domingo V, Amarenco P, Bousser MG. Ischemic stroke in a sportsman who consumed MaHuang extract and creatine monohydrate for bodybuilding. J Neurol Neurosurg Psychiatr 2000;68:112-3.
- Wakabayashi K, Kono S, Shinchi K, et al. Habitual coffee consumption and blood pressure: A study of self-defense officials in Japan. Eur J Epidemiol 1998;14:669-73. PubMed
- Hodgson JM, Puddey IB, Burke V, et al. Effects on blood pressure of drinking green and black tea. J Hypertens 1999;17:457-63. PubMed
- Booth SL, Madabushi HT, Davidson KW, et al. Tea and coffee brews are not dietary sources of vitamin K-1 (phylloquinone). J Am Diet Assoc 1995;95:82-3. PubMed
- Lou FQ, Zhang MF, Zhang XG, et al. A study on tea-pigment in prevention of atherosclerosis. Chin Med J (Engl) 1989;102:579-83.
- Graham HN. Green tea composition, consumption, and polyphenol chemistry. Prev Med 1992;21:334-50. PubMed
- Rapuri PB, Gallagher JC, Kinyamu HK, Ryschon KL. Caffeine intake increases the rate of bone loss in elderly women and interacts with vitamin D receptor genotypes. Am J Clin Nutr 2001;74:694-700. PubMed
- The National Toxicology Program (NTP). Caffeine. Center for the Evaluation of Risks to Human Reproduction (CERHR). Available at: http://cerhr.niehs.nih.gov/common/caffeine.html.
- Klebanoff MA, Levine RJ, DerSimonian R, et al. Maternal serum paraxanthine, a caffeine metabolite, and the risk of spontaneous abortion. N Engl J Med 1999;341:1639-44. PubMed
- Eskenazi B. Caffeine—filtering the facts. N Engl J Med 1999;341:1688-9. PubMed
- Fernandes O, Sabharwal M, Smiley T, et al. Moderate to heavy caffeine consumption during pregnancy and relationship to spontaneous abortion and abnormal fetal growth: a meta-analysis. Reprod Toxicol 1998;12:435-44. PubMed
- Pollock BG, Wylie M, Stack JA, et al. Inhibition of caffeine metabolism by estrogen replacement therapy in postmenopausal women. J Clin Pharmacol 1999;39:936-40. PubMed
- Dews PB, Curtis GL, Hanford KJ, O'Brien CP. The frequency of caffeine withdrawal in a population-based survey and in a controlled, blinded pilot experiment. J Clin Pharmacol 1999;39:1221-32. PubMed
- FDA. Proposed rule: dietary supplements containing ephedrine alkaloids. Available at: www.verity.fda.gov (Accessed 25 January 2000).
- Weisburger JH. Tea and health: the underlying mechanisms. Proc Soc Exp Biol Med 1999;220:271-5. PubMed
- Taylor JR, Wilt VM. Probable antagonism of warfarin by green tea. Ann Pharmacother 1999;33:426-8. PubMed
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Hagg S, Spigset O, Mjorndal T, Dahlqvist R. Effect of caffeine on clozapine pharmacokinetics in healthy volunteers. Br J Clin Pharmacol 2000;49:59-63. PubMed
- Watson JM, Jenkins EJ, Hamilton P, et al. Influence of caffeine on the frequency and perception of hypoglycemia in free-living patients with type 1 diabetes. Diabetes Care 2000;23:455-9. PubMed
- Lloyd T, Johnson-Rollings N, Eggli DF, et al. Bone status among postmenopausal women with different habitual caffeine intakes: a longitudinal investigation. J Am Coll Nutr 2000;19:256-61. PubMed
- American Academy of Pediatrics. The transfer of drugs and other chemicals into human milk. Pediatrics 2001;108:776-89. PubMed
- Heck AM, DeWitt BA, Lukes AL. Potential interactions between alternative therapies and warfarin. Am J Health Syst Pharm 2000;57:1221-7. DOI
- Sinclair CJ, Geiger JD. Caffeine use in sports. A pharmacological review. J Sports Med Phys Fitness 2000;40:71-9.
- Haller CA, Benowitz NL. Adverse cardiovascular and central nervous system events associated with dietary supplements containing ephedra alkaloids. N Engl J Med 2000;343:1833-8. PubMed
- Ali M, Afzal M. A potent inhibitor of thrombin stimulated platelet thromboxane formation from unprocessed tea. Prostaglandins Leukot Med 1987;27:9-13. PubMed
- Ardlie NG, Glew G, Schultz BG, Schwartz CJ. Inhibition and reversal of platelet aggregation by methyl xanthines. Thromb Diath Haemorrh 1967;18:670-3. DOI
- Ferrini RL, Barrett-Connor E. Caffeine intake and endogenous sex steroid levels in postmenopausal women. The Rancho Bernardo Study. Am J Epidemiol 1996:144:642-4. PubMed
- Pisters KM, Newman RA, Coldman B, et al. Phase I trial of oral green tea extract in adult patients with solid tumors. J Clin Oncol 2001;19:1830-8. PubMed
- Haller CA, Jacob P 3rd, Benowitz NL. Pharmacology of ephedra alkaloids and caffeine after single-dose dietary supplement use. Clin Pharmacol Ther 2002;71:421-32. PubMed
- Bell DG, Jacobs I, Ellerington K. Effect of caffeine and ephedrine ingestion on anaerobic exercise performance. Med Sci Sports Exerc 2001;33:1399-403. PubMed
- Horner NK, Lampe JW. Potential mechanisms of diet therapy for fibrocystic breast conditions show inadequate evidence of effectiveness. J Am Diet Assoc 2000;100:1368-80. PubMed
- Bracken MB, Triche EW, Belanger K, et al. Association of maternal caffeine consumption with decrements in fetal growth. Am J Epidemiol 2003;157:456-66.. PubMed
- McGowan JD, Altman RE, Kanto WP Jr. Neonatal withdrawal symptoms after chronic maternal ingestion of caffeine. South Med J 1988;81:1092-4.. PubMed
- Nehlig A, Debry G. Consequences on the newborn of chronic maternal consumption of coffee during gestation and lactation: a review. J Am Coll Nutr 1994;13:6-21.. PubMed
- Massey LK. Is caffeine a risk factor for bone loss in the elderly? Am J Clin Nutr 2001;74:569-70. PubMed
- Kockler DR, McCarthy MW, Lawson CL. Seizure activity and unresponsiveness after hydroxycut ingestion. Pharmacotherapy 2001;21:647-51.. PubMed
- Nix D, Zelenitsky S, Symonds W, et al. The effect of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. Clin Pharmacol Ther 1992;51:183. DOI
- Ahn WS, Yoo J, Huh SW, et al. Protective effects of green tea extracts (polyphenon E and EGCG) on human cervical lesions. Eur J Cancer Prev 2003;12:383-90. PubMed
- Infante S, Baeza ML, Calvo M, et al. Anaphylaxis due to caffeine. Allergy 2003;58:681-2. PubMed
- Massey LK, Whiting SJ. Caffeine, urinary calcium, calcium metabolism and bone. J Nutr 1993;123:1611-4. PubMed
- Shirai T, Hayakawa H, Akiyama J, et al. Food allergy to green tea. J Allergy Clin Immunol 2003;112:805-6. PubMed
- Jatoi A, Ellison N, Burch PA, et al. A phase II trial of green tea in the treatment of patients with androgen independent metastatic prostate carcinoma. Cancer 2003;97:1442-6.. PubMed
- Nawrot P, Jordan S, Eastwood J, et al. Effects of caffeine on human health. Food Addit Contam 2003;20:1-30. PubMed
- May DC, Jarboe CH, VanBakel AB, Williams WM. Effects of cimetidine on caffeine disposition in smokers and nonsmokers. Clin Pharmacol Ther 1982;31:656-61. PubMed
- Brown NJ, Ryder D, Branch RA. A pharmacodynamic interaction between caffeine and phenylpropanolamine. Clin Pharmacol Ther 1991;50:363-71. PubMed
- Sanderink GJ, Bournique B, Stevens J, et al. Involvement of human CYP1A isoenzymes in the metabolism and drug interactions of riluzole in vitro. Pharmacol Exp Ther 1997;282:1465-72. DOI
- Wahllander A, Paumgartner G. Effect of ketoconazole and terbinafine on the pharmacokinetics of caffeine in healthy volunteers. Eur J Clin Pharmacol 1989;37:279-83. PubMed
- Carrillo JA, Benitez J. Clinically significant pharmacokinetic interactions between dietary caffeine and medications. Clin Pharmacokinet 2000;39:127-53. PubMed
- Underwood DA. Which medications should be held before a pharmacologic or exercise stress test? Cleve Clin J Med 2002;69:449-50. PubMed
- Aqel RA, Zoghbi GJ, Trimm JR, et al. Effect of caffeine administered intravenously on intracoronary-administered adenosine-induced coronary hemodynamics in patients with coronary artery disease. Am J Cardiol 2004;93:343-6. PubMed
- Zheng XM, Williams RC. Serum caffeine levels after 24-hour abstention: clinical implications on dipyridamole (201)Tl myocardial perfusion imaging. J Nucl Med Technol 2002;30:123-7.
- Institute of Medicine. Caffeine for the Sustainment of Mental Task Performance: Formulations for Military Operations. Washington, DC: National Academy Press, 2001. Available at: http://books.nap.edu/books/0309082587/html/index.html. DOI
- Dews PB, O'Brien CP, Bergman J. Caffeine: behavioral effects of withdrawal and related issues. Food Chem Toxicol 2002;40:1257-61. PubMed
- Beach CA, Mays DC, Guiler RC, et al. Inhibition of elimination of caffeine by disulfiram in normal subjects and recovering alcoholics. Clin Pharmacol Ther 1986;39:265-70. PubMed
- Yang YC, Lu FH, Wu JS, et al. The protective effect of habitual tea consumption on hypertension. Arch Intern Med 2004 26;164:1534-40. PubMed
- Son DJ, Cho MR, Jin YR, et al. Antiplatelet effect of green tea catechins: a possible mechanism through arachidonic acid pathway. Prostaglandins Leukot Essent Fatty Acids 2004;71:25-31. PubMed
- Juliano LM, Griffiths RR. A critical review of caffeine withdrawal: empirical validation of symptoms and signs, incidence, severity, and associated features. Psychopharmacology (Berl) 2004;176:1-29. PubMed
- Winkelmayer WC, Stampfer MJ, Willett WC, Curhan GC. Habitual caffeine intake and the risk of hypertension in women. JAMA 2005;294:2330-5. PubMed
- Raaska K, Raitasuo V, Laitila J, Neuvonen PJ. Effect of caffeine-containing versus decaffeinated coffee on serum clozapine concentrations in hospitalised patients. Basic Clin Pharmacol Toxicol 2004;94:13-8. DOI
- Forrest WH Jr, Bellville JW, Brown BW Jr. The interaction of caffeine with pentobarbital as a nighttime hypnotic. Anesthesiology 1972;36:37-41. PubMed
- Lake CR, Rosenberg DB, Gallant S, et al. Phenylpropanolamine increases plasma caffeine levels. Clin Pharmacol Ther 1990;47:675-85. PubMed
- Bonkovsky HL. Hepatotoxicity associated with supplements containing Chinese green tea (Camellia sinensis). Ann Intern Med 2006;144:68-71.
- Gloro R, Hourmand-Ollivier I, Mosquet B, et al. Fulminant hepatitis during self-medication with hydroalcoholic extract of green tea. Eur J Gastroenterol Hepatol 2005;17:1135-7. PubMed
- Donovan JL, Chavin KD, Devane CL, et al. Green tea (Camellia sinensis) extract does not alter cytochrome P450 3A4 or 2D6 activity in healthy volunteers. Drug Metab Dispos 2004;32:906-8. PubMed
- Chu KO, Wang CC, Chu CY, et al. Pharmacokinetic studies of green tea catechins in maternal plasma and fetuses in rats. J Pharm Sci 2006;95:1372-81. PubMed
- Isbrucker RA, Edwards JA, Wolz E, et al. Safety studies on epigallocatechin gallate (EGCG) preparations. Part 3: teratogenicity and reproductive toxicity studies in rats. Food Chem Toxicol 2006;44:651-61. PubMed
- Navarro-Peran E, Cabezas-Herrera J, Garcia-Canovas F, et al. The antifolate activity of tea catechins. Cancer Res 2005;65:2059-64. PubMed
- Jimenez-Saenz M, Martinez-Sanchez, MDC. Acute hepatitis associated with the use of green tea infusions. J Hepatol 2006;44:616-9. PubMed
- Bradley Pharmaceuticals. Veregen Prescribing Information. October 2006.
- Correa A, Stolley A, Liu Y. Prenatal tea consumption and risks of anencephaly and spina bifida. Ann Epidemiol 2000;10:476-7. PubMed
- Weng X, Odouli R, Li DK. Maternal caffeine consumption during pregnancy and the risk of miscarriage: a prospective cohort study. Am J Obstet Gynecol 2008;198:279.e1-8. PubMed
- Savitz DA, Chan RL, Herring AH, et al. Caffeine and miscarriage risk. Epidemiology 2008;19:55-62. PubMed
- Golden ED, Lam PY, Kardosh A, et al. Green tea polyphenols block the anticancer effects of bortezomib and other boronic acid-based proteasome inhibitors. Blood 2009;113:5927-37. PubMed
- Misaka S, Yatabe J, Muller F, et al. Green Tea Ingestion Greatly Reduces Plasma Concentrations of Nadolol in Healthy Subjects. Clin Pharmacol Ther 2014. [Epub ahead of print]. PubMed
- Roth M, Timmermann BN, Hagenbuch B. Interactions of green tea catechins with organic anion-transporting polypeptides. Drug Metab Dispos 2011;39:920-6. PubMed
- Kato Y, Miyazaki T, Kano T, et al. Involvement of influx and efflux transport systems in gastrointestinal absorption of celiprolol. J Pharm Sci 2009;98:2529-39. PubMed
- Chan, H. T., So, L. T., Li, S. W., Siu, C. W., Lau, C. P., and Tse, H. F. Effect of herbal consumption on time in therapeutic range of warfarin therapy in patients with atrial fibrillation. J.Cardiovasc.Pharmacol. 2011;58(1):87-90. PubMed
- Nishikawa, M., Ariyoshi, N., Kotani, A., Ishii, I., Nakamura, H., Nakasa, H., Ida, M., Nakamura, H., Kimura, N., Kimura, M., Hasegawa, A., Kusu, F., Ohmori, S., Nakazawa, K., and Kitada, M. Effects of continuous ingestion of green tea or grape seed extrac
- Shet, M. S., McPhaul, M., Fisher, C. W., Stallings, N. R., and Estabrook, R. W. Metabolism of the antiandrogenic drug (Flutamide) by human CYP1A2. Drug Metab Dispos. 1997;25(11):1298-1303.
- Staib, A. H., Stille, W., Dietlein, G., Shah, P. M., Harder, S., Mieke, S., and Beer, C. Interaction between quinolones and caffeine. Drugs 1987;34 Suppl 1:170-174. PubMed
- Stille, W., Harder, S., Mieke, S., Beer, C., Shah, P. M., Frech, K., and Staib, A. H. Decrease of caffeine elimination in man during co-administration of 4-quinolones. J.Antimicrob.Chemother. 1987;20(5):729-734. PubMed
- Fuhr, U., Strobl, G., Manaut, F., Anders, E. M., Sorgel, F., Lopez-de-Brinas, E., Chu, D. T., Pernet, A. G., Mahr, G., Sanz, F., and . Quinolone antibacterial agents: relationship between structure and in vitro inhibition of the human cytochrome P450 isof
- Kot, M. and Daniel, W. A. Effect of diethyldithiocarbamate (DDC) and ticlopidine on CYP1A2 activity and caffeine metabolism: an in vitro comparative study with human cDNA-expressed CYP1A2 and liver microsomes. Pharmacol Rep. 2009;61(6):1216-1220. PubMed
- Gasior, M., Borowicz, K., Buszewicz, G., Kleinrok, Z., and Czuczwar, S. J. Anticonvulsant activity of phenobarbital and valproate against maximal electroshock in mice during chronic treatment with caffeine and caffeine discontinuation. Epilepsia 1996;37(3 PubMed
- Jankiewicz, K., Chroscinska-Krawczyk, M., Blaszczyk, B., and Czuczwar, S. J. [Caffeine and antiepileptic drugs: experimental and clinical data]. Przegl.Lek. 2007;64(11):965-967.
- Luszczki, J. J., Zuchora, M., Sawicka, K. M., Kozinska, J., and Czuczwar, S. J. Acute exposure to caffeine decreases the anticonvulsant action of ethosuximide, but not that of clonazepam, phenobarbital and valproate against pentetrazole-induced seizures i
- Chroscinska-Krawczyk, M., Jargiello-Baszak, M., Walek, M., Tylus, B., and Czuczwar, S. J. Caffeine and the anticonvulsant potency of antiepileptic drugs: experimental and clinical data. Pharmacol.Rep. 2011;63(1):12-18. PubMed
- Vaz, J., Kulkarni, C., David, J., and Joseph, T. Influence of caffeine on pharmacokinetic profile of sodium valproate and carbamazepine in normal human volunteers. Indian J.Exp.Biol. 1998;36(1):112-114.
- Gasior, M., Swiader, M., Przybylko, M., Borowicz, K., Turski, W. A., Kleinrok, Z., and Czuczwar, S. J. Felbamate demonstrates low propensity for interaction with methylxanthines and Ca2+ channel modulators against experimental seizures in mice. Eur.J Phar PubMed
- Mohiuddin, M., Azam, A. T., Amran, M. S., and Hossain, M. A. In vive effects of gliclazide and metformin on the plasma concentration of caffeine in healthy rats. Pak.J Biol Sci 5-1-2009;12(9):734-737.
- Mays, D. C., Camisa, C., Cheney, P., Pacula, C. M., Nawoot, S., and Gerber, N. Methoxsalen is a potent inhibitor of the metabolism of caffeine in humans. Clin.Pharmacol.Ther. 1987;42(6):621-626. PubMed
- Wojcikowski, J. and Daniel, W. A. Perazine at therapeutic drug concentrations inhibits human cytochrome P450 isoenzyme 1A2 (CYP1A2) and caffeine metabolism--an in vitro study. Pharmacol Rep. 2009;61(5):851-858. PubMed
- Daniel, W. A., Syrek, M., Rylko, Z., and Kot, M. Effects of phenothiazine neuroleptics on the rate of caffeine demethylation and hydroxylation in the rat liver. Pol.J Pharmacol 2001;53(6):615-621.
- Norager, C. B., Jensen, M. B., Weimann, A., and Madsen, M. R. Metabolic effects of caffeine ingestion and physical work in 75-year old citizens. A randomized, double-blind, placebo-controlled, cross-over study. Clin Endocrinol (Oxf) 2006;65(2):223-228. PubMed
- Wang, X. and Yeung, J. H. Effects of the aqueous extract from Salvia miltiorrhiza Bunge on caffeine pharmacokinetics and liver microsomal CYP1A2 activity in humans and rats. J Pharm Pharmacol 2010;62(8):1077-1083.
- Kot M, Daniel WA. Caffeine as a marker substrate for testing cytochrome P450 activity in human and rat. Pharmacol Rep 2008;60:789-97.
- Kjaerstad MB, Nielsen F, Nohr-Jensen L, et al. Systemic uptake of miconazole during vaginal suppository use and effect on CYP1A2 and CYP3A4 associated enzyme activities in women. Eur J Clin Pharmacol 2010;66:1189-97. PubMed
- Goh BC, Reddy NJ, Dandamudi UB, et al. An evaluation of the drug interaction potential of pazopanib, an oral vascular endothelial growth factor receptor tyrosine kinase inhibitor, using a modified Cooperstown 5+1 cocktail in patients with advanced solid t
- Chen Y, Kang Z, Yan J, et al. Liu wei di huang wan, a well-known traditional Chinese medicine induces CYP1A2 while suppressing CYP2A6 and N-acetyltransferase 2 acivities in man. J Ethnopharmacol 2010;132:213-8.
- Suzuki S, Murayama Y, Sugiyama E, et al. Estimating pediatric doses of drugs metabolized by cytochrome P450 (CYP) isozymes, based on physiological liver development and serum protein levels. Yakugaku Zasshi 2010;130:613-20. PubMed
- Chien CF, Wu YT, Lee WC, et al. Herb-drug interaction of Andrographis paniculata extract and andrographolide on the pharmacokinetics of theophylline in rats. Chem Biol Interact 2010;184:458-65. PubMed
- Mills BM, Zaya MJ, Walters RR, et al. Current cytochrome P450 phenotyping methods applied to metabolic drug -drug interaction prediction in dogs. Drug Metab Dispos 2010;38:396-404. PubMed
- Turpault S, Brian W, Van Horn R, et al. Pharmacokinetic assessment of a five-probe cocktail for CYPs 1A2, 2C9, 2C19, 2D6, and 3A. Br J Clin Pharmacol 2009;68:928-35. PubMed
- Filimonova AA, Ziganshina LE, Ziganshin AU, Chichirov AA. On the possibility of patient phenotyping on the basis of cytochrome p-450 1A2 isoenzyme activity using caffeine as the test substrate. Eksp Klin Farmakol 2009;72:61-5.
- Jenkins J, Williams D, Deng Y, et al. Eltrombopag, an oral thrombopoietin receptor agonist, has no impact on the pharmacokinetic profile of probe drugs for cytochrome P450 isoenzymes CYP3A4, CYP1A2, CYP2C9 and CYP2C19 in healthy men: a cocktail analysis.
- Chow, H. H., Cai, Y., Hakim, I. A., Crowell, J. A., Shahi, F., Brooks, C. A., Dorr, R. T., Hara, Y., and Alberts, D. S. Pharmacokinetics and safety of green tea polyphenols after multiple-dose administration of epigallocatechin gallate and polyphenon E i
- Gross, G., Meyer, K. G., Pres, H., Thielert, C., Tawfik, H., and Mescheder, A. A randomized, double-blind, four-arm parallel-group, placebo-controlled Phase II/III study to investigate the clinical efficacy of two galenic formulations of Polyphenon E in
- Stockfleth, E., Beti, H., Orasan, R., Grigorian, F., Mescheder, A., Tawfik, H., and Thielert, C. Topical Polyphenon E in the treatment of external genital and perianal warts: a randomized controlled trial. Br.J Dermatol. 2008;158(6):1329-1338.
- Smits, P., Temme, L., and Thien, T. The cardiovascular interaction between caffeine and nicotine in humans. Clin Pharmacol Ther 1993;54(2):194-204. PubMed
- MacKenzie, T., Comi, R., Sluss, P., Keisari, R., Manwar, S., Kim, J., Larson, R., and Baron, J. A. Metabolic and hormonal effects of caffeine: randomized, double-blind, placebo-controlled crossover trial. Metabolism 2007;56(12):1694-1698. PubMed
- Lopez-Garcia, E., Rodriguez-Artalejo, F., Rexrode, K. M., Logroscino, G., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of stroke in women. Circulation 3-3-2009;119(8):1116-1123. PubMed
- Zhang, W., Lopez-Garcia, E., Li, T. Y., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of cardiovascular diseases and all-cause mortality among men with type 2 diabetes. Diabetes Care 2009;32(6):1043-1045. PubMed
- Moisey, L. L., Robinson, L. E., and Graham, T. E. Consumption of caffeinated coffee and a high carbohydrate meal affects postprandial metabolism of a subsequent oral glucose tolerance test in young, healthy males. Br.J Nutr. 2010;103(6):833-841. PubMed
- Chroscinska-Krawczyk, M., Ratnaraj, N., Patsalos, P. N., and Czuczwar, S. J. Effect of caffeine on the anticonvulsant effects of oxcarbazepine, lamotrigine and tiagabine in a mouse model of generalized tonic-clonic seizures. Pharmacol Rep. 2009;61(5):819 PubMed
- Simmonds, M. J., Minahan, C. L., and Sabapathy, S. Caffeine improves supramaximal cycling but not the rate of anaerobic energy release. Eur.J Appl Physiol 2010;109(2):287-295. PubMed
- Buscemi, S., Verga, S., Batsis, J. A., Donatelli, M., Tranchina, M. R., Belmonte, S., Mattina, A., Re, A., and Cerasola, G. Acute effects of coffee on endothelial function in healthy subjects. Eur.J Clin Nutr. 2010;64(5):483-489. PubMed
- Rigato, I., Blarasin, L., and Kette, F. Severe hypokalemia in 2 young bicycle riders due to massive caffeine intake. Clin J Sport Med. 2010;20(2):128-130. PubMed
- Ernest, D., Chia, M., and Corallo, C. E. Profound hypokalaemia due to Nurofen Plus and Red Bull misuse. Crit Care Resusc. 2010;12(2):109-110. DOI
- Conen, D., Chiuve, S. E., Everett, B. M., Zhang, S. M., Buring, J. E., and Albert, C. M. Caffeine consumption and incident atrial fibrillation in women. Am J Clin Nutr 2010;92(3):509-514. PubMed
- Reis, J. P., Loria, C. M., Steffen, L. M., Zhou, X., van, Horn L., Siscovick, D. S., Jacobs, D. R., Jr., and Carr, J. J. Coffee, decaffeinated coffee, caffeine, and tea consumption in young adulthood and atherosclerosis later in life: the CARDIA study. A PubMed
- Clausen, T. Hormonal and pharmacological modification of plasma potassium homeostasis. Fundam.Clin Pharmacol 2010;24(5):595-605. PubMed
- Gronroos, N. N. and Alonso, A. Diet and risk of atrial fibrillation - epidemiologic and clinical evidence -. Circ.J 2010;74(10):2029-2038. PubMed
- Perera, V., Gross, A. S., and McLachlan, A. J. Caffeine and paraxanthine HPLC assay for CYP1A2 phenotype assessment using saliva and plasma. Biomed.Chromatogr. 2010;24(10):1136-1144. PubMed
- Orozco-Gregorio, H., Mota-Rojas, D., Bonilla-Jaime, H., Trujillo-Ortega, M. E., Becerril-Herrera, M., Hernandez-Gonzalez, R., and Villanueva-Garcia, D. Effects of administration of caffeine on metabolic variables in neonatal pigs with peripartum asphyxia PubMed
- Izzo, A. A. and Ernst, E. Interactions between herbal medicines and prescribed drugs: an updated systematic review. Drugs 2009;69(13):1777-1798. PubMed
- Laurie, S. A., Miller, V. A., Grant, S. C., Kris, M. G., and Ng, K. K. Phase I study of green tea extract in patients with advanced lung cancer. Cancer Chemother.Pharmacol. 2005;55(1):33-38. PubMed
- Chiu, A. E., Chan, J. L., Kern, D. G., Kohler, S., Rehmus, W. E., and Kimball, A. B. Double-blinded, placebo-controlled trial of green tea extracts in the clinical and histologic appearance of photoaging skin. Dermatol Surg. 2005;31(7 Pt 2):855-860. PubMed
- Javaid, A. and Bonkovsky, H. L. Hepatotoxicity due to extracts of Chinese green tea (Camellia sinensis): a growing concern. J Hepatol 2006;45(2):334-335. PubMed
- Martinez-Sierra, C., Rendon, Unceta P., and Martin, Herrera L. [Acute hepatitis after green tea ingestion]. Med Clin (Barc.) 6-17-2006;127(3):119.
- Molinari, M., Watt, K. D., Kruszyna, T., Nelson, R., Walsh, M., Huang, W. Y., Nashan, B., and Peltekian, K. Acute liver failure induced by green tea extracts: case report and review of the literature. Liver Transpl. 2006;12(12):1892-1895. PubMed
- Chow, H. H., Hakim, I. A., Vining, D. R., Crowell, J. A., Cordova, C. A., Chew, W. M., Xu, M. J., Hsu, C. H., Ranger-Moore, J., and Alberts, D. S. Effects of repeated green tea catechin administration on human cytochrome P450 activity. Cancer Epidemiol.B PubMed
- Federico, A., Tiso, A., and Loguercio, C. A case of hepatotoxicity caused by green tea. Free Radic.Biol Med 8-1-2007;43(3):474. PubMed
- Sarma, D. N., Barrett, M. L., Chavez, M. L., Gardiner, P., Ko, R., Mahady, G. B., Marles, R. J., Pellicore, L. S., Giancaspro, G. I., and Low, Dog T. Safety of green tea extracts : a systematic review by the US Pharmacopeia. Drug Saf 2008;31(6):469-484. PubMed
- Engdal, S. and Nilsen, O. G. In vitro inhibition of CYP3A4 by herbal remedies frequently used by cancer patients. Phytother.Res. 2009;23(7):906-912.
- Bergman, J. and Schjott, J. Hepatitis caused by Lotus-f3? Basic Clin Pharmacol.Toxicol. 2009;104(5):414-416. PubMed
- Kalus, U., Kiesewetter, H., and Radtke, H. Effect of CYSTUS052 and green tea on subjective symptoms in patients with infection of the upper respiratory tract. Phytother.Res. 2010;24(1):96-100.
- Tatti, S., Stockfleth, E., Beutner, K. R., Tawfik, H., Elsasser, U., Weyrauch, P., and Mescheder, A. Polyphenon E: a new treatment for external anogenital warts. Br.J Dermatol. 2010;162(1):176-184.
- Tsao, A. S., Liu, D., Martin, J., Tang, X. M., Lee, J. J., El-Naggar, A. K., Wistuba, I., Culotta, K. S., Mao, L., Gillenwater, A., Sagesaka, Y. M., Hong, W. K., and Papadimitrakopoulou, V. Phase II randomized, placebo-controlled trial of green tea extra
- Liatsos, G. D., Moulakakis, A., Ketikoglou, I., and Klonari, S. Possible green tea-induced thrombotic thrombocytopenic purpura. Am.J Health Syst.Pharm. 4-1-2010;67(7):531-534. PubMed
- Josic, J., Olsson, A. T., Wickeberg, J., Lindstedt, S., and Hlebowicz, J. Does green tea affect postprandial glucose, insulin and satiety in healthy subjects: a randomized controlled trial. Nutr.J. 2010;9:63. PubMed
- Miller, R. J., Jackson, K. G., Dadd, T., Mayes, A. E., Brown, A. L., and Minihane, A. M. The impact of the catechol-O-methyltransferase genotype on the acute responsiveness of vascular reactivity to a green tea extract. Br.J.Nutr. 2011;105(8):1138-1144.
- Rohde, J., Jacobsen, C., and Kromann-Andersen, H. [Toxic hepatitis triggered by green tea]. Ugeskr.Laeger 1-17-2011;173(3):205-206.
- Tzellos, T. G., Sardeli, C., Lallas, A., Papazisis, G., Chourdakis, M., and Kouvelas, D. Efficacy, safety and tolerability of green tea catechins in the treatment of external anogenital warts: a systematic review and meta-analysis. J.Eur.Acad.Dermatol.Ve PubMed
- Otera, H., Tada, K., Sakurai, T., Hashimoto, K., and Ikeda, A. Hypersensitivity pneumonitis associated with inhalation of catechin-rich green tea extracts. Respiration 2011;82(4):388-392. PubMed
- Yellapu, R. K., Mittal, V., Grewal, P., Fiel, M., and Schiano, T. Acute liver failure caused by 'fat burners' and dietary supplements: a case report and literature review. Can.J.Gastroenterol. 2011;25(3):157-160. PubMed
- Karth, A., Holoshitz, N., Kavinsky, C. J., Trohman, R., and McBride, B. F. A case report of atrial fibrillation potentially induced by hydroxycut: a multicomponent dietary weight loss supplement devoid of sympathomimetic amines. J.Pharm.Pract. 2010;23(3) PubMed
- Hsu, C. H., Liao, Y. L., Lin, S. C., Tsai, T. H., Huang, C. J., and Chou, P. Does supplementation with green tea extract improve insulin resistance in obese type 2 diabetics? A randomized, double-blind, and placebo-controlled clinical trial. Altern.Med.R
- Zheng XX, Xu YL, Li SH, et al. Green tea intake lowers fasting serum total and LDL cholesterol in adults: a meta-analysis of 14 randomized controlled trials. Am.J.Clin.Nutr. 2011;94:601-610. PubMed
- Miller, R. J., Jackson, K. G., Dadd, T., Mayes, A. E., Brown, A. L., Lovegrove, J. A., and Minihane, A. M. The impact of the catechol-O-methyltransferase genotype on vascular function and blood pressure after acute green tea ingestion. Mol.Nutr.Food Res.
- Bogdanski, P., Suliburska, J., Szulinska, M., Stepien, M., Pupek-Musialik, D., and Jablecka, A. Green tea extract reduces blood pressure, inflammatory biomarkers, and oxidative stress and improves parameters associated with insulin resistance in obese, h
- Jurgens, T. M., Whelan, A. M., Killian, L., Doucette, S., Kirk, S., and Foy, E. Green tea for weight loss and weight maintenance in overweight or obese adults. Cochrane.Database.Syst.Rev. 2012;12:CD008650. PubMed
- Sakamoto, O., Saita, N., Yamasaki, H., Tamanoi, M., and Ando, M. Pulmonary granulomatosis caused by aspirated green tea. Chest 1994;106(1):308-309. PubMed
- Jiménez-Encarnación E, Ríos G, Muñoz-Mirabal A, Vilá LM. Euforia-induced acute hepatitis in a patient with scleroderma. BMJ Case Rep 2012;2012. PubMed
- Choi JS, Burm JP. Effects of oral epigallocatechin gallate on the pharmacokinetics of nicardipine in rats. Arch Pharm Res. 2009 Dec;32(12):1721-5. PubMed
- Chung JH, Choi DH, Choi JS. Effects of oral epigallocatechin gallate on the oral pharmacokinetics of verapamil in rats. Biopharm Drug Dispos. 2009 Mar;30(2):90-3. PubMed
- Crew KD, Brown P, Greenlee H, Bevers TB, Arun B, Hudis C, McArthur HL, Chang J, Rimawi M, Vornik L, Cornelison TL, Wang A, Hibshoosh H, Ahmed A, Terry MB, Santella RM, Lippman SM, Hershman DL. Phase IB randomized, double-blinded, placebo-controlled, dose
- Dryden GW, Lam A, Beatty K, Qazzaz HH, McClain CJ. A pilot study to evaluate the safety and efficacy of an oral dose of (-)-epigallocatechin-3-gallate-rich polyphenon E in patients with mild to moderate ulcerative colitis. Inflamm Bowel Dis. 2013 Aug;19(9 PubMed
- Gallo E, Maggini V, Berardi M, Pugi A, Notaro R, Talini G, Vannozzi G, Bagnoli S, Forte P, Mugelli A, Annese V, Firenzuoli F, Vannacci A. Is green tea a potential trigger for autoimmune hepatitis? Phytomedicine. 2013 Oct 15;20(13):1186-9. PubMed
- Liu K, Zhou R, Wang B, Chen K, Shi LY, Zhu JD, Mi MT. Effect of green tea on glucose control and insulin sensitivity: a meta-analysis of 17 randomized controlled trials. Am J Clin Nutr. 2013 Aug;98(2):340-8. PubMed
- Onakpoya I, Spencer E, Heneghan C, Thompson M. The effect of green tea on blood pressure and lipid profile: a systematic review and meta-analysis of randomized clinical trials. Nutr Metab Cardiovasc Dis. 2014 Aug;24:823-36. PubMed
- Patel SS, Beer S, Kearney DL, Phillips G, Carter BA. Green tea extract: a potential cause of acute liver failure. World J Gastroenterol. 2013 Aug 21;19(31):5174-7. PubMed
- Pillukat MH, Bester C, Hensel A, Lechtenberg M, Petereit F, Beckebaum S, Müller KM, Schmidt HH. Concentrated green tea extract induces severe acute hepatitis in a 63-year-old woman--a case report with pharmaceutical analysis. J Ethnopharmacol. 2014 Aug 8; PubMed
- Schönthal AH. Adverse effects of concentrated green tea extracts. Mol Nutr Food Res. 2011 Jun;55(6):874-85. PubMed
- Shiraishi M, Haruna M, Matsuzaki M, Ota E, Murayama R, Murashima S. Association between the serum folate levels and tea consumption during pregnancy. Biosci Trends. 2010 Oct;4(5):225-30.
- Jang EH, Choi JY, Park CS, Lee SK, Kim CE, Park HJ, Kang JS, Lee JW, Kang JH. Effects of green tea extract administration on the pharmacokinetics of clozapine in rats. J Pharm Pharmacol. 2005 Mar;57(3):311-6. PubMed
- Trudel D, Labbé DP, Araya-Farias M, Doyen A, Bazinet L, Duchesne T, Plante M, Grégoire J, Renaud MC, Bachvarov D, Têtu B, Bairati I. A two-stage, single-arm, phase II study of EGCG-enriched green tea drink as a maintenance therapy in women with advanced s
- Zheng XX, Xu YL, Li SH, Hui R, Wu YJ, Huang XH. Effects of green tea catechins with or without caffeine on glycemic control in adults: a meta-analysis of randomized controlled trials. Am J Clin Nutr. 2013 Apr;97(4):750-62. PubMed
- Caldeira D, Martins C, Alves LB, Pereira H, Ferreira JJ, Costa J. Caffeine does not increase the risk of atrial fibrillation: a systematic review and meta-analysis of observational studies. Heart. 2013;99(19):1383-9. doi: 10.1136/heartjnl-2013-303950. Re PubMed
- Cheng M, Hu Z, Lu X, Huang J, Gu D. Caffeine intake and atrial fibrillation incidence: dose response meta-analysis of prospective cohort studies. Can J Cardiol. 2014 Apr;30(4):448-54. doi: 10.1016/j.cjca.2013.12.026. Epub 2014 2. Review. PubMed
- van der Hoeven N, Visser I, Schene A, van den Born BJ. Severe hypertension related to caffeinated coffee and tranylcypromine: a case report. Ann Intern Med. 2014 May 6;160(9):657-8. doi: 10.7326/L14-5009-8. No abstract available. PubMed
- Dixit S, Stein PK, Dewland TA, Dukes JW, Vittinghoff E, Heckbert SR, Marcus GM. Consumption of Caffeinated Products and Cardiac Ectopy. J Am Heart Assoc. 2016 26;5(1). pii: e002503. doi: 10.1161/JAHA.115.002503. PubMed
- Health Canada. Health Product Info Watch. October 2016; 5-6. Available at: http://www.hc-sc.gc.ca/dhp-mps/medeff/bulletin/hpiw-ivps_2016-10-eng.php#a15.
- Green Tea Extract-Containing Natural Health Products - Rare Risk of Serious Liver Injury. Recalls & alerts. November 15, 2017. http://healthycanadians.gc.ca/recall-alert-rappel-avis/hc-sc/2017/65100a-eng.php. Accessed November 10, 2017.
- Mazzanti G, Di Sotto A, Vitalone A. Hepatotoxicity of green tea: an update. Arch Toxicol. 2015;89(8):1175-91. PubMed
- Isomura T, Suzuki S, Origasa H, et al. Liver-related safety assessment of green tea extracts in humans: a systematic review of randomized controlled trials. Eur J Clin Nutr. 2016;70(11):1221-1229. PubMed
- Drug Record: Green Tea (Camellia Sinesis). LiverTox: National Institutes of Health, U.S. Department of Health & Human Services, March 2014. https://livertox.nlm.nih.gov//GreenTea.htm. Accessed November 20, 2017.
- Yates AA, Erdman JW Jr, Shao A, Dolan LC, Griffiths JC. Bioactive nutrients - Time for tolerable upper intake levels to address safety. Regul Toxicol Pharmacol. 2017;84:94-101. PubMed
- Younes M, Aggett P, Aguilar F, et al. EFSA Panel on Food Additives and Nutrient Sources added to Food (ANS). Scientific opinion on the safety of green tea catechins. EFSA Journal 2018;16(4):5239. PubMed
- Zuchinali P, Riberio PA, Pimentel M, da Rosa PR, Zimerman LI, Rohde LE. Effect of caffeine on ventricular arrhythmia: a systematic review and meta-analysis of experimental and clinical studies. Europace 2016 Feb;18(2):257-66. PubMed
- Dostal AM, Samavat H, Bedell S, et al. The safety of green tea extract supplementation in postmenopausal women at risk for breast cancer: results of the Minnesota Green Tea Trial. Food Chem Toxicol. 2015 Sep;83:26-35. PubMed
- Shamekhi Z, Amani R, Habibagahi Z, Namjoyan F, Ghadiri A, Saki Malehi A. A Randomized, Double-blind, Placebo-controlled Clinical Trial Examining the Effects of Green Tea Extract on Systemic Lupus Erythematosus Disease Activity and Quality of Life. Phytoth PubMed
- Lagier D, Nee L, Guieu R, et al. Peri-operative oral caffeine does not prevent postoperative atrial fibrillation after heart valve surgery with cardiopulmonary bypass: a randomized controlled clinical trial. Eur J Anaesthesiol. 2018 Apr 26. [Epub ahead of DOI
- Voskoboinik A, Kalman JM, Kistler PM. Caffeine and arrhythmias: time to grind the data. JACC: Clin Electrophysiol. 2018;4(4):425-32. PubMed
- Chong SJ, Howard KA, Knox C. Hypokalaemia and drinking green tea: a literature review and report of 2 cases. BMJ Case Rep. 2016;2016. pii: bcr2016214425. PubMed
- Qiao J, Gu C, Shang W, et al. Effect of green tea on pharmacokinetics of 5-fluorouracil in rats and pharmacodynamics in human cell lines in vitro. Food Chem Toxicol. 2011;49(6):1410-5. PubMed
- Abe O, Ono T, Sato H, et al. Role of (-)-epigallocatechin gallate in the pharmacokinetic interaction between nadolol and green tea in healthy volunteers. Eur J Clin Pharmacol 2018;74(6):775-83. doi: 10.1007/s00228-018-2436-2. PubMed
- Wikoff D, Welsh BT, Henderson R, et al. Systematic review of the potential adverse effects of caffeine consumption in healthy adults, pregnant women, adolescents, and children. Food Chem Toxicol 2017;109:585-648. PubMed
- Nutescu EA, Shapiro NL, Ibrahim S, et al. Warfarin and its interactions with foods, herbs and other dietary supplements. Expert Opin Drug Saf. 2006;5(3):433-51. PubMed
- Abdelkawy KS, Abdelaziz RM, Abdelmageed AM, Donia AM, El-Khodary NM. Effects of green tea extract on atorvastatin pharmacokinetics in healthy volunteers. Eur J Drug Metab Pharmacokinet. 2020;45(3):351-360. PubMed
- Filippini T, Malavolti M, Borrelli F, et al. Green tea (Camellia sinensis) for the prevention of cancer. Cochrane Database Syst Rev. 2020;3(3):CD005004. PubMed
- Huang S, Xu Q, Liu L, et al. Effect of green tea and (-)-epigallocatechin gallate on the pharmacokinetics of rosuvastatin. Curr Drug Metab. 2020. PubMed
- Mahmoodi M, Hosseini R, Kazemi A, Ofori-Asenso R, Mazidi M, Mazloomi SM. Effects of green tea or green tea catechin on liver enzymes in healthy individuals and people with nonalcoholic fatty liver disease: A systematic review and meta-analysis of randomiz
- Misaka S, Abe O, Ono T, et al. Effects of single green tea ingestion on pharmacokinetics of nadolol in healthy volunteers. Br J Clin Pharmacol. 2020. PubMed
- Oketch-Rabah HA, Roe AL, Rider CV, et al. United States Pharmacopeia (USP) comprehensive review of the hepatotoxicity of green tea extracts. Toxicol Rep. 2020;7:386-402. PubMed
- Kim TE, Ha N, Kim Y, et al. Effect of epigallocatechin-3-gallate, major ingredient of green tea, on the pharmacokinetics of rosuvastatin in healthy volunteers. Drug Des Devel Ther. 2017;11:1409-1416. PubMed
- Misaka S, Ono Y, Uchida A, et al. Impact of green tea catechin ingestion on the pharmacokinetics of lisinopril in healthy volunteers. Clin Transl Sci. 2020. PubMed
- Darweesh RS, El-Elimat T, Zayed A, et al. The effect of grape seed and green tea extracts on the pharmacokinetics of imatinib and its main metabolite, N-desmethyl imatinib, in rats. BMC Pharmacol Toxicol. 2020;21(1):77. PubMed
- Sonoda J, Ogata K, Yoshikawa N, Sato K, Ikeda R, Shimodozono Y. Impact of green tea intake on the pharmacokinetics of celiprolol in healthy subjects. Int J Clin Pharmacol Ther. 2020. PubMed
- Kim S, Park TH, Kim WI, Park S, Kim JH, Cho MK. The effects of green tea on acne vulgaris: A systematic review and meta-analysis of randomized clinical trials. Phytother Res. 2021;35(1):374-383. PubMed
- Percevault S, Charpiat B, Lebossé F, Mabrut JY, Vial T, Colom M. Green tea and hepatoxicity: Two case reports. Therapie 2021. PubMed
- Kajita N, Miyama S, Kinoshita K, Yoshida K, Narita M. Green tea-induced anaphylaxis: The first pediatric case report. Allergol Int 2021;70(4):507-508. PubMed
- Zheng KH, Zhu K, Wactawski-Wende J, et al. Caffeine intake from coffee and tea and invasive breast cancer incidence among postmenopausal women in the Women's Health Initiative. Int J Cancer 2021;149(12):2032-2044. PubMed
- Wang S, Li X, Yang Y, et al. Does coffee, tea and caffeine consumption reduce the risk of incident breast cancer? A systematic review and network meta-analysis. Public Health Nutr 2021;24(18):6377-6389. PubMed
- Alshabi AM, Alkahtani SA, Shaikh IA, Habeeb MS. Caffeine modulates pharmacokinetic and pharmacodynamic profiles of pioglitazone in diabetic rats: Impact on therapeutics. Saudi Med J 2021;42(2):151-160. PubMed
- Gleason JL, Sundaram R, Mitro SD, et al. Association of maternal caffeine consumption during pregnancy with child growth. JAMA Netw Open. 2022;5(10):e2239609. PubMed
- Seufferlein T, Ettrich TJ, Menzler S, et al. Green tea extract to prevent colorectal adenomas, results of a randomized, placebo-controlled clinical trial. Am J Gastroenterol 2022;117(6):884-894. PubMed
- Teramoto M, Yamagishi K, Muraki I, Tamakoshi A, Iso H. Coffee and green tea consumption and cardiovascular disease mortality among people with and without hypertension. J Am Heart Assoc 2023;12(2):e026477. PubMed
- Veerman GDM, van der Werff SC, Koolen SLW, et al. The influence of green tea extract on nintedanib's bioavailability in patients with pulmonary fibrosis. Biomed Pharmacother 2022;151:113101. PubMed
- Misaka S, Ono Y, Taudte RV, et al. Exposure of fexofenadine, but not pseudoephedrine, is markedly decreased by green tea extract in healthy volunteers. Clin Pharmacol Ther 2022;112(3):627-634. PubMed
- Zhao H, Zhu W, Zhao X, et al. Efficacy of epigallocatechin-3-gallate in preventing dermatitis in patients with breast cancer receiving postoperative radiotherapy: A double-blind, placebo-controlled, phase 2 randomized clinical trial. JAMA Dermatol 2022;15 PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC