
Essential for Men Ingredients & Drug Interactions
by Ritual
What is this page for?
First and foremost: checking Essential for Men against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Essential for Men is a dietary supplement by Ritual with 10 active ingredients. Its ingredients are commonly taken for treating or preventing b12 deficiency, pernicious anemia, low energy and fatigue.Based on those ingredients, 1,274 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Vitamin E, Vitamin D, Vitamin A. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Essential for Men by Ritual
Ask about any prescription or over-the-counter medication and we check it for interactions with Essential for Men by Ritual — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Essential for Men by Ritual
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
Essential for Men contains 10 active ingredients: vitamin B12, vitamin K2, vitamin A, boron, magnesium, zinc, folate, vitamin D, vitamin E, and omega-3 fatty acids. The product also includes several inactive ingredients—cellulose, corn zein, hypromellose, gellan gum, and silica—which are used as fillers and capsule materials.
Each ingredient serves a specific nutritional role. B12 supports energy and nerve function, K2 supports bone and cardiovascular health, vitamin A supports vision and immune function, magnesium and zinc support dozens of enzymatic and immune processes, vitamin D regulates calcium and bone health, vitamin E acts as an antioxidant, folate supports DNA synthesis, boron supports bone metabolism, and omega-3 fatty acids support heart and brain health.
Does it work?
Moderate evidence
Effectiveness varies by ingredient and intended use. Vitamin B12 is effective for B12 deficiency and treating certain neurological conditions, and likely effective for cyanide poisoning.
Vitamin K2 is effective for clotting factor deficiencies and possibly effective for osteoporosis. Vitamin A is effective for A deficiency and possibly effective for aging skin, measles, and ulcerative colitis.
Magnesium is effective for constipation and indigestion, and for correcting magnesium deficiency and pre-eclampsia. Zinc is effective for zinc deficiency and likely effective for Wilson disease, and possibly effective for acne and age-related macular degeneration.
Vitamin D is effective for rickets, osteomalacia, and related bone disorders. Vitamin E is effective for E deficiency and possibly effective for Alzheimer disease.
Boron is likely effective for boron deficiency and possibly effective for vaginal yeast infections. We do not hold effectiveness data for folate or omega-3 fatty acids in our records.
How safe is it?
Well-documented data
Most of these ingredients are generally well tolerated at recommended doses. Vitamin B12 is very safe—excess is removed in urine and there is no established upper limit.
Vitamin K2 is generally safe in food and supplement amounts, though your doctor should approve supplements. Magnesium commonly causes mild diarrhea, nausea, or stomach upset at higher doses.
Zinc at recommended levels is well tolerated, though it can cause a metallic taste, nausea, or diarrhea. Vitamin D is safe at recommended doses but can cause toxicity at very high doses.
Vitamin A at high doses (above the tolerable upper limit) can cause serious liver damage, headache, skin problems, and birth defects—pregnant people should avoid high doses. Vitamin E at high doses may increase bleeding risk.
Boron should be avoided in pregnancy and breastfeeding due to limited safety data and potential fetal harm at high amounts. No adverse effect or pregnancy/breastfeeding data are on file for folate or omega-3 fatty acids in this product record.
Magnesium and vitamin D are considered needed in pregnancy at normal recommended amounts; if you are pregnant, check with your doctor before taking this product. If you are breastfeeding, consult your provider about use of supplements.
Meds to double-check
Major interaction found
Before taking this product, check with your pharmacist or use the medication checker below if you take warfarin or any other blood thinner (vitamin K2 and A can reduce their effect), levodopa/carbidopa for Parkinson's disease (magnesium decreases its levels), skeletal muscle relaxants, potassium-sparing diuretics, calcium channel blockers for heart rhythm or blood pressure, tetracycline or quinolone antibiotics, other antibiotics including cephalexin, bisphosphonates for bone health, HIV medications including ritonavir or integrase inhibitors, thiazide diuretics, heart rhythm drugs like verapamil or digoxin, statins like atorvastatin, or any chemotherapy drug. These are the main medication types documented to interact with ingredients in this supplement.
The bottom line
Scorecard at a glanceFully disclosed formula with some supporting evidence for its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
This is a multivitamin formulated for men's nutritional support. If you take any prescription medications—especially blood thinners, diabetes drugs, antibiotics, heart medications, or Parkinson's medication—check your exact drugs with the tool on this page before starting.
Pregnant or breastfeeding people should talk with their doctor first. If you have any liver disease, are on high-dose vitamin A, or have a history of bleeding, mention this product to your pharmacist.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 9 of 10 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Nov 22, 2024.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Essential for Men, straight from the product label.
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
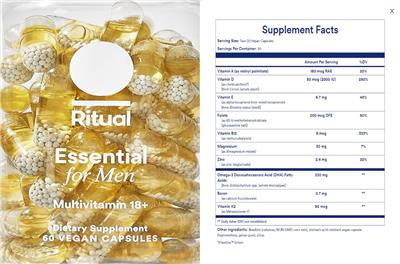
Supplement Facts
The label details for Essential for Men by Ritual, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Vitamin B12 | 8 mcg | 333% |
| Vitamin K2 | 90 mcg | -- |
| Vitamin A | 180 mcg RAE | 20% |
| Boron | 0.7 mg | -- |
| Magnesium | 30 mg | 7% |
| Zinc | 2.4 mg | 22% |
| Folate | 200 mcg DFE | 50% |
| Vitamin D | 50 mcg | 250% |
| Vitamin E | 6.7 mg | 45% |
| Omega-3 Fatty Acids | 330 mg | -- |
Other ingredients: Cellulose, Corn Zein, Hypromellose, Gellan Gum, Silica
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formula
Essential for men
Precautions
Multivitamin 18+
FDA Statement of Identity
Dietary Supplement
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Essential for Men by Ritual label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Essential for Men by Ritual
These are the 10 active ingredients this product is made of. Select any to open its full monograph.
Serving size2 Vegan Capsule(s) Dosage formCapsule Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Vitamin B12
Interacts with20 drugs
Vitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very h...
Vitamin B12 monograph & interactionsVitamin K2
Interacts with2 drugs
Vitamin K is an essential nutrient your body needs for normal blood clotting and to support healthy bones. Most people get enough from food, but suppl...
Vitamin K2 monograph & interactionsVitamin A
Interacts with387 drugs
Vitamin A is an essential nutrient important for vision, skin, immune function, and growth. Most people get enough from a balanced diet, and supplemen...
Vitamin A monograph & interactionsBoron
No knowninteractions
Boron is a trace mineral found in many plant foods and sold as a supplement, mainly promoted for bone, joint, and hormone health. The human evidence f...
Boron monograph & interactionsMagnesium
Interacts with295 drugs
Magnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preven...
Magnesium monograph & interactionsZinc
Interacts with67 drugs
Zinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but suppleme...
Zinc monograph & interactionsFolate
Vitamin D
Interacts with715 drugs
Vitamin D is a fat-soluble vitamin that helps your body absorb calcium and is important for healthy bones, muscles, and immune function. Many people,...
Vitamin D monograph & interactionsVitamin E
Interacts with764 drugs
Vitamin E is an essential fat-soluble vitamin and antioxidant that most people get in adequate amounts from a normal diet. Supplements can help correc...
Vitamin E monograph & interactionsOmega-3 Fatty Acids
Interacts with375 drugs
DHA is an omega-3 fatty acid found in fatty fish and algae that is a building block for the brain, nervous system, and eyes. It is widely used and gen...
Omega-3 Fatty Acids monograph & interactionsOther (inactive) ingredients: Cellulose, Corn Zein, Hypromellose, Gellan Gum, Silica. These complete the product’s ingredient list but are not active constituents.
Essential for Men by Ritual Drug Interactions
HelloPharmacist Interaction Report
Essential for Men by Ritual contains several ingredients that interact with common medications.
The most serious interaction is with warfarin (Coumadin), a blood thinner: both vitamin K2 and vitamin A can reduce warfarin's effectiveness by interfering with how your body processes it. Vitamin K2 is the major concern here—even moderate amounts can antagonize warfarin's blood-thinning effects.
Read the full breakdown — every affected drug type, severity by severity
Other significant interactions span multiple drug categories. Magnesium can reduce the effectiveness of levodopa/carbidopa (Parkinson's medication) and may enhance the effects of skeletal muscle relaxants, potassium-sparing diuretics, and calcium channel blockers used for heart rhythm or blood pressure.
It can also interfere with quinolone and other antibiotics, as well as bisphosphonates for bone health. Zinc similarly reduces absorption of quinolone antibiotics, tetracyclines, cephalexin, and penicillamine, and may decrease levels of HIV medications like ritonavir and integrase inhibitors.
Vitamin A at high doses poses risks with retinoid medications (acne and psoriasis treatments), potentially hepatotoxic drugs, tetracycline antibiotics, and warfarin. Vitamin D at high doses can raise calcium levels dangerously when combined with thiazide diuretics, and may reduce effectiveness of certain heart medications and statins.
Vitamin E can increase bleeding risk with blood thinners and antiplatelet drugs, and may interfere with some chemotherapy and with niacin's cholesterol benefits.
Vitamin B12 has a minor interaction with metformin (diabetes medication), which can lower B12 levels with long-term use. Boron, folate, and omega-3 fatty acids were not checked for drug interactions in our data, or we hold no monograph for them.
Altogether, these interactions span 1,126 individual medications. Because this product contains multiple ingredients with documented interactions, please use the medication checker below to search your specific prescriptions before starting.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Essential for Men?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Essential for Men interact with 1,274 drugs. Click any drug to see the details.
8 of the 10 ingredients in Essential for Men interact with drugs. Each result below shows which ingredient is responsible. Vitamin E Vitamin D Vitamin A Omega-3 Fatty Acids Magnesium Zinc Vitamin B12 Vitamin K2
AcitretinSoriatane
How Acitretin interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Acitretin interactionAlitretinoinPanretin
How Alitretinoin interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Alitretinoin interactionBenserazide, LevodopaMadopar, Prolopa
How Benserazide, Levodopa interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Benserazide, Levodopa interactionBexaroteneTargretin
How Bexarotene interacts with Essential for Men — through 3 ingredients. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Bexarotene interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Bexarotene interactionVitamin DCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D + Bexarotene interactionCarbidopaLodosyn
How Carbidopa interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa interactionCarbidopa, LevodopaDhivy, Rytary, Sinemet, Sinemet CR
How Carbidopa, Levodopa interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa, Levodopa interactionCarbidopa, Levodopa, EntacaponeStalevo
How Carbidopa, Levodopa, Entacapone interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa, Levodopa, Entacapone interactionHalobetasol Propionate,tazaroteneDuobrii
How Halobetasol Propionate,tazarotene interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Halobetasol Propionate,tazarotene interactionIsotretinoinAbsorica, Accutane, Amnesteem, Claravis, Roaccutane, Sotret
How Isotretinoin interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Isotretinoin interactionLevodopaInbrija, Larodopa
How Levodopa interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Levodopa interactionLevodopa, CarbidopaDuodopa
How Levodopa, Carbidopa interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Levodopa, Carbidopa interactionTazaroteneArazlo, Avage, Fabior, Tazorotene, Zorac
How Tazarotene interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Tazarotene interactionTretinoinAltreno, Renova, Retin-A, Vesanoid
How Tretinoin interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Tretinoin interactionTretinoin, Benzoyl PeroxideTwyneo
How Tretinoin, Benzoyl Peroxide interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Tretinoin, Benzoyl Peroxide interactionWarfarinWarfarin
How Warfarin interacts with Essential for Men — through 6 ingredients. Tap an ingredient for the detail:
Vitamin K2Warfarin (coumadin) Major
Interaction Summary
Vitamin K can antagonize and reverse the therapeutic effects of warfarin.
Read the full Vitamin K2 + Warfarin interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Warfarin interactionOmega-3 Fatty AcidsAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, DHA may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Omega-3 Fatty Acids + Warfarin interactionVitamin AWarfarin (coumadin) Moderate
Interaction Summary
Theoretically, high doses of vitamin A could increase the risk of bleeding with warfarin.
Read the full Vitamin A + Warfarin interactionVitamin DCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D + Warfarin interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Warfarin interactionWarfarin SodiumCoumadin, Panwarfin, Sofarin
How Warfarin Sodium interacts with Essential for Men — through 6 ingredients. Tap an ingredient for the detail:
Vitamin K2Warfarin (coumadin) Major
Interaction Summary
Vitamin K can antagonize and reverse the therapeutic effects of warfarin.
Read the full Vitamin K2 + Warfarin Sodium interactionVitamin EAnticoagulant/antiplatelet Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Read the full Vitamin E + Warfarin Sodium interactionOmega-3 Fatty AcidsAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, DHA may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Omega-3 Fatty Acids + Warfarin Sodium interactionVitamin AWarfarin (coumadin) Moderate
Interaction Summary
Theoretically, high doses of vitamin A could increase the risk of bleeding with warfarin.
Read the full Vitamin A + Warfarin Sodium interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Warfarin Sodium interactionVitamin DCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D + Warfarin Sodium interactionEtretinateTegison
How Etretinate interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Etretinate interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with Essential for Men — through 2 ingredients. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Ado-trastuzumab Emtansine interactionVitamin DCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with Essential for Men — through 1 ingredient. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Abacavir, Lamivudine interactionAbciximabReoPro
How Abciximab interacts with Essential for Men — through 3 ingredients. Tap an ingredient for the detail:
Vitamin EAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Read the full Vitamin E + Abciximab interactionOmega-3 Fatty AcidsAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, DHA may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Omega-3 Fatty Acids + Abciximab interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with Essential for Men — through 2 ingredients. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Abemaciclib interactionVitamin DCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D + Abemaciclib interactionAbiraterone
How Abiraterone interacts with Essential for Men — through 3 ingredients. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Abiraterone interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Abiraterone interactionVitamin DCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with Essential for Men — through 3 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Abiraterone Acetate interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Abiraterone Acetate interactionVitamin DCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with Essential for Men — through 3 ingredients. Tap an ingredient for the detail:
Vitamin EAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Read the full Vitamin E + Abrocitinib interactionOmega-3 Fatty AcidsAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, DHA may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Omega-3 Fatty Acids + Abrocitinib interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with Essential for Men — through 2 ingredients. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acalabrutinib interactionVitamin DCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Essential for Men — through 2 ingredients. Tap an ingredient for the detail:
Omega-3 Fatty AcidsAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking DHA with antidiabetes drugs might reduce the effects of these medications.
Read the full Omega-3 Fatty Acids + Acarbose interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Essential for Men — through 2 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Acebutolol interactionOmega-3 Fatty AcidsAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking DHA with antihypertensive drugs might increase the risk of hypotension.
Read the full Omega-3 Fatty Acids + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Essential for Men — through 3 ingredients. Tap an ingredient for the detail:
Vitamin EAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Read the full Vitamin E + Acenocoumarol interactionOmega-3 Fatty AcidsAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, DHA may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Omega-3 Fatty Acids + Acenocoumarol interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Acenocoumarol interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Essential for Men with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Vitamin E
Alkylating Agents
Theoretically, antioxidant effects of vitamin E might reduce the effectiveness of alkylating agents.
There's concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin E have on chemotherapy. Advise patients to consult their oncologist before using vitamin E supplements, especially in high doses.
Anticoagulant/Antiplatelet Drugs
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Vitamin E seems to inhibit of platelet aggregation and antagonize the effects of vitamin K-dependent clotting factors. These effects appear to be dose-dependent, and are probably only likely to be clinically significant with doses of at least 800 units daily. Mixed tocopherols, such as those found in food, might have a greater antiplatelet effect than alpha-tocopherol. RRR alpha-tocopherol (natural vitamin E) 1000 IU daily antagonizes vitamin K-dependent clotting factors. Advise patients to avoid high doses of vitamin E, especially in people with low vitamin K intake or other risk factors for bleeding.
Antitumor Antibiotics
Theoretically, antioxidant effects of vitamin E might reduce the effectiveness of antitumor antibiotics.
There's concern that antioxidants could reduce the activity of antitumor antibiotic drugs such as doxorubicin, which generate free radicals. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin E have on chemotherapy involving antitumor antibiotics. Advise patients to consult their oncologist before using vitamin E supplements, especially in high doses.
Cyclosporine (Neoral, Sandimmune)
A specific form of vitamin E might increase absorption and levels of cyclosporine.
There is some evidence that one specific formulation of vitamin E (D-alpha-tocopheryl-polyethylene glycol-1000 succinate, TPGS, tocophersolan, Liqui-E) might increase absorption of cyclosporine. This vitamin E formulation forms micelles which seems to increase absorption of cyclosporine by 40% to 72% in some patients. However, this interaction is unlikely to occur with the usual forms of vitamin E.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Vitamin E appears to bind with the nuclear receptor, pregnane X receptor (PXR), which results in increased expression of CYP3A4. Although the clinical significance of this is not known, use caution when considering concomitant use of vitamin E and other drugs affected by these enzymes.
Selumetinib (Koselugo)
Taking selumetinib with vitamin E can result in a total daily dose of vitamin E that exceeds safe limits and therefore might increase the risk of bleeding.
Selumetinib contains 48-54 IU vitamin E per capsule. The increased risk of bleeding with vitamin E appears to be dose-dependent. Be cautious when using selumetinib in combination with supplemental vitamin E, especially in patients at higher risk of bleed, such as those with chronic conditions and those taking antiplatelet drugs.
Warfarin (Coumadin)
Using vitamin E with warfarin might increase the risk of bleeding.
Due to interference with production of vitamin K-dependent clotting factors, use of more than 400 IU of vitamin E daily with warfarin might increase prothrombin time (PT), INR, and the risk of bleeding,. At a dose of 1000 IU per day, vitamin E can antagonize vitamin K-dependent clotting factors even in people not taking warfarin. Limited clinical evidence suggests that doses up to 1200 IU daily may be used safely by patients taking warfarin, but this may not be applicable in all patient populations.
Niacin
Vitamin E might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises high-density lipoprotein (HDL) cholesterol levels in people with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50%. Vitamin E alone combined with a statin does not seem to decrease HDL levels. It is not known whether the adverse effect on HDL is due to one of the other antioxidants or to the combination. It also is not known whether it will occur in other patient populations.
Vitamin D
Aluminum
Vitamin D might increase aluminum absorption and toxicity, but this has only been reported in people with renal failure.
The protein that transports calcium across the intestinal wall can also bind and transport aluminum. This protein is stimulated by vitamin D, which may therefore increase aluminum absorption. This mechanism may contribute to increased aluminum levels and toxicity in people with renal failure, when they take vitamin D and aluminum-containing phosphate binders chronically.
Atorvastatin (Lipitor)
Vitamin D might reduce absorption of atorvastatin.
A small, low-quality clinical study shows that taking vitamin D reduces levels of atorvastatin and its active metabolites by up to 55%. However, while atorvastatin levels decreased, total cholesterol, low-density lipoprotein (LDL) cholesterol, and high-density lipoprotein (HDL) cholesterol levels did not substantially change. Atorvastatin is metabolized in the gut by CYP3A4 enzymes, and researchers theorized that vitamin D might induce CYP3A4, causing reduced levels of atorvastatin. However, this proposed mechanism was not specifically studied.
Calcipotriene (Dovonex)
Taking calcipotriene with vitamin D increases the risk for hypercalcemia.
Calcipotriene is a vitamin D analog used topically for psoriasis. It can be absorbed in sufficient amounts to cause systemic effects, including hypercalcemia. Theoretically, combining calcipotriene with vitamin D supplements might increase the risk of hypercalcemia.
Digoxin (Lanoxin)
Theoretically, hypercalcemia induced by high-dose vitamin D can increase the risk of arrhythmia from digoxin.
High doses of vitamin D can cause hypercalcemia. Hypercalcemia increases the risk of fatal cardiac arrhythmias with digoxin. Avoid vitamin D doses above the tolerable upper intake level (4000 IU daily for adults) and monitor serum calcium levels in people taking vitamin D and digoxin concurrently.
Diltiazem (Cardizem, Others)
Theoretically, hypercalcemia induced by high-dose vitamin D can reduce the therapeutic effects of diltiazem for arrhythmia.
High doses of vitamin D can cause hypercalcemia. Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically this could also occur with diltiazem. Avoid vitamin D doses above the tolerable upper intake level (4000 IU daily for adults) and monitor serum calcium levels in people taking vitamin D and diltiazem concurrently.
Thiazide Diuretics
Theoretically, taking thiazide diuretics and high-dose vitamin D can increase the risk of hypercalcemia.
Thiazide diuretics decrease urinary calcium excretion, which could lead to hypercalcemia if vitamin D supplements are taken concurrently. This has been reported in people being treated with vitamin D for hypoparathyroidism, and also in elderly people with normal parathyroid function who were taking a thiazide, vitamin D, and calcium-containing antacids daily.
Verapamil (Calan, Others)
Hypercalcemia induced by high-dose vitamin D can reduce the therapeutic effects of verapamil for arrhythmia.
Hypercalcemia due to high doses of vitamin D can reduce the effectiveness of verapamil in atrial fibrillation. Avoid vitamin D doses above the tolerable upper intake level (4000 IU daily for adults) and monitor serum calcium levels in people taking vitamin D and verapamil concurrently.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
There is some concern that vitamin D might induce CYP3A4. In vitro research suggests that vitamin D induces CYP3A4 transcription. Additionally, observational research has found that increased UV light exposure and serum vitamin D levels are associated with decreased serum levels of CYP3A4 substrates such as tacrolimus and sirolimus, while no association between UV light exposure or vitamin D levels and levels of mycophenolic acid, a non-CYP3A4 substrate, was found. A small, low-quality clinical study shows that taking vitamin D reduces levels of the CYP3A4 substrate atorvastatin and its active metabolites by up to 55%; however, the clinical effects of atorvastatin were not reduced. While researchers theorized that vitamin D might induce CYP3A4, this proposed mechanism was not specifically studied.
Vitamin A
Retinoids
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Retinoids, which are vitamin A derivatives, could have additive toxic effects when taken with vitamin A supplements.
Hepatotoxic Drugs
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
The tolerable upper intake level (UL) is the highest level of intake that is likely to pose no risk of adverse effects. Doses of vitamin A above the UL can cause hepatotoxicity, ranging from elevated liver enzymes to liver failure.
Tetracycline Antibiotics
Theoretically, taking tetracycline antibiotics with high doses of vitamin A can increase the risk of pseudotumor cerebri.
Benign intracranial hypertension (pseudotumor cerebri) can occur with tetracyclines and with acute or chronic vitamin A toxicity. Case reports suggest that taking tetracyclines and vitamin A concurrently can increase the risk of this condition. Avoid high doses of vitamin A in people taking tetracyclines chronically.
Warfarin (Coumadin)
Theoretically, high doses of vitamin A could increase the risk of bleeding with warfarin.
Vitamin A toxicity is associated with hemorrhage and hypoprothrombinemia, possibly due to vitamin K antagonism. Advise patients taking warfarin to avoid doses of vitamin A above the tolerable upper intake level of 10,000 IU/day for adults.
Omega-3 Fatty Acids
Anticoagulant/Antiplatelet Drugs
Theoretically, DHA may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Although some clinical evidence suggests that DHA might reduce collagen-stimulated platelet aggregation and thromboxane release, most clinical evidence suggests that DHA alone does not affect blood clotting. However, theoretically, when given in combination with EPA as fish oil, concomitant use with anticoagulant or antiplatelet drugs (including aspirin) might increase risk of bleeding.
Antidiabetes Drugs
Theoretically, taking DHA with antidiabetes drugs might reduce the effects of these medications.
In people with type 2 diabetes, including those taking oral hypoglycemic medications, DHA seems to increase fasting blood glucose levels.
Antihypertensive Drugs
Theoretically, taking DHA with antihypertensive drugs might increase the risk of hypotension.
Fish oils containing DHA can lower blood pressure and might have additive effects in patients treated with antihypertensives; use with caution.
Magnesium
Levodopa/Carbidopa (Sinemet)
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Clinical research in healthy volunteers shows that taking magnesium oxide 1000 mg with levodopa 100 mg/carbidopa 10 mg reduces the area under the curve (AUC) of levodopa by 35% and of carbidopa by 81%. In vitro and animal research shows that magnesium produces an alkaline environment in the digestive tract, which might lead to degradation and reduced bioavailability of levodopa/carbidopa.
Aminoglycoside Antibiotics
Concomitant use of aminoglycoside antibiotics and magnesium can increase the risk for neuromuscular weakness.
Both aminoglycosides and magnesium reduce presynaptic acetylcholine release, which can lead to neuromuscular blockade and possible paralysis. This is most likely to occur with high doses of magnesium given intravenously.
Antacids
Use of acid reducers may reduce the laxative effect of magnesium oxide.
A retrospective analysis shows that, in the presence of H2 receptor antagonists (H2RAs) or proton pump inhibitors (PPIs), a higher dose of magnesium oxide is needed for a laxative effect. This may also occur with antacids. Under acidic conditions, magnesium oxide is converted to magnesium chloride and then to magnesium bicarbonate, which has an osmotic laxative effect. By reducing acidity, antacids may reduce the conversion of magnesium oxide to the active bicarbonate salt.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after magnesium containing products.
Bisphosphonates
Magnesium can decrease absorption of bisphosphonates.
Cations, including magnesium, can decrease bisphosphonate absorption. Advise patients to separate doses of magnesium and these drugs by at least 2 hours.
Calcium Channel Blockers
Magnesium can have additive effects with calcium channel blockers, although evidence is conflicting.
Magnesium inhibits calcium entry into smooth muscle cells and may therefore have additive effects with calcium channel blockers. Severe hypotension and neuromuscular blockades may occur when nifedipine is used with intravenous magnesium, although some contradictory evidence suggests that concurrent use of magnesium with nifedipine does not increase the risk of neuromuscular weakness. High doses of magnesium could theoretically have additive effects with other calcium channel blockers.
Digoxin
Magnesium salts may reduce absorption of digoxin.
Clinical evidence suggests that treatment with oral magnesium hydroxide or magnesium trisilicate reduces absorption of digoxin from the intestines. This may reduce the blood levels of digoxin and decrease its therapeutic effects.
Potassium-Sparing Diuretics
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Potassium-sparing diuretics also have magnesium-sparing properties, which can counteract the magnesium losses associated with loop and thiazide diuretics. Theoretically, increased magnesium levels could result from concomitant use of potassium-sparing diuretics and magnesium supplements.
Quinolone Antibiotics
Magnesium decreases absorption of quinolones.
Magnesium can form insoluble complexes with quinolones and decrease their absorption. Advise patients to take these drugs at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Skeletal Muscle Relaxants
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Parenteral magnesium shortens the time to onset of skeletal muscle relaxants by about 1 minute and prolongs the duration of action by about 2 minutes. Magnesium potentiates the effects of skeletal muscle relaxants by decreasing calcium-mediated release of acetylcholine from presynaptic nerve terminals, reducing postsynaptic sensitivity to acetylcholine, and having a direct effect on the membrane potential of myocytes. Magnesium also has vasodilatory actions and increases cardiac output, allowing a greater amount of muscle relaxant to reach the motor end plate. A clinical study found that low-dose rocuronium (0.45 mg/kg), when given after administration of magnesium 30 mg/kg over 10 minutes, has an accelerated onset of effect, which matches the onset of effect seen with a full-dose rocuronium regimen (0.6 mg/kg). In another clinical study, onset times for rocuronium doses of 0.3, 0.6, and 1.2 mg/kg were 86, 76, and 50 seconds, respectively, when given alone, but were reduced to 66, 44, and 38 seconds, respectively, when the doses were given after a 15-minute infusion of magnesium sulfate 60 mg/kg. Giving intraoperative intravenous magnesium sulfate, 50 mg/kg loading dose followed by 15 mg/kg/hour, reduces the onset time of rocuronium, enhances its clinical effects, reduces the dose of intraoperative opiates, and prolongs the spontaneous recovery time. It does not affect the activity of subsequently administered neostigmine.
Sulfonylureas
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Clinical research shows that administration of magnesium hydroxide with glyburide increases glyburide absorption, increases maximal insulin response by 35-fold, and increases the risk of hypoglycemia, when compared with glyburide alone. A similar interaction occurs between magnesium hydroxide and glipizide. The mechanism of this effect appears to be related to the elevation of gastrointestinal pH by magnesium-based antacids, increasing solubility and enhancing absorption of sulfonylureas.
Tetracycline Antibiotics
Magnesium decreases absorption of tetracyclines.
Magnesium can form insoluble complexes with tetracyclines in the gut and decrease their absorption and antibacterial activity. Advise patients to take these drugs 1 hour before or 2 hours after magnesium supplements.
Anticoagulant/Antiplatelet Drugs
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
In vitro evidence shows that magnesium sulfate inhibits platelet aggregation, even at low concentrations. Some preliminary clinical evidence shows that infusion of magnesium sulfate increases bleeding time by 48% and reduces platelet activity. However, other clinical research shows that magnesium does not affect platelet aggregation, although inhibition of platelet-dependent thrombosis can occur.
Gabapentin (Neurontin)
Gabapentin absorption can be decreased by magnesium.
Clinical research shows that giving magnesium oxide orally along with gabapentin decreases the maximum plasma concentration of gabapentin by 33%, time to maximum concentration by 36%, and area under the curve by 43%. Advise patients to take gabapentin at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Sevelamer (Renagel, Renvela)
Sevelamer may increase serum magnesium levels.
In patients on hemodialysis, sevelamer use was associated with a 0.28 mg/dL increase in serum magnesium. The mechanism of this interaction remains unclear.
Zinc
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Theoretically, zinc might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after zinc containing products.
Cephalexin (Keflex)
Zinc might decrease cephalexin levels by chelating with cephalexin in the gut and preventing its absorption.
A pharmacokinetic study shows that zinc sulfate 250 mg taken concomitantly with cephalexin 500 mg decreases peak levels of cephalexin by 31% and reduces the exposure to cephalexin by 27%. Also, taking zinc sulfate 3 hours before cephalexin decreases peak levels of cephalexin by 11% and reduces the exposure to cephalexin by 18%. By decreasing cephalexin levels, zinc might increase the risk of treatment failure. This effect does not occur when zinc is taken 3 hours after the cephalexin dose. To avoid an interaction, advise patients take zinc sulfate 3 hours after taking cephalexin.
Cisplatin (Platinol-Aq)
Theoretically, zinc might interfere with the therapeutic effects of cisplatin.
Animal research suggests that zinc stimulates tumor cell production of the protein metallothionein, which binds and inactivates cisplatin. It is not known whether zinc supplements or high dietary zinc intake can cause clinically significant interference with cisplatin therapy. Cisplatin might also increase zinc excretion.
Integrase Inhibitors
Theoretically, taking zinc along with integrase inhibitors might decrease the levels and clinical effects of these drugs.
Zinc is a divalent cation. Pharmacokinetic studies have shown that other divalent cations such as calcium and iron can decrease blood levels of the integrase inhibitor dolutegravir through chelation.
Penicillamine (Cuprimine, Depen)
Zinc might reduce the levels and clinical effects of penicillamine.
By forming an insoluble complex with penicillamine, zinc interferes with penicillamine absorption and activity. Zinc supplements reduce the efficacy of low-dose penicillamine (0.5-1 gram/day), but do not seem to affect higher doses (1-2.75 gram/day), provided dosing times are separated. Advise patients to take zinc and penicillamine at least 2 hours apart.
Quinolone Antibiotics
Zinc can decrease the levels and clinical effects of quinolones antibiotics.
Quinolones form complexes with zinc in the gastrointestinal tract, reducing absorption of both the quinolone and zinc if taken at the same time. Advise patients to take these drugs at least 2 hours before, or 4-6 hours after, zinc supplements.
Ritonavir (Norvir)
Zinc modestly reduces levels of ritonavir.
Clinical research shows that zinc might reduce serum ritonavir levels by chelating with ritonavir in the gut and preventing its absorption. In patients with HIV, ritonavir is taken with atazanavir to prevent the metabolism and increase the effects of atazanavir. A pharmacokinetic study shows that, in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate (Solvazinc tablets) 125 mg as a single dose or as multiple daily doses for 2 weeks reduces plasma levels of ritonavir by about 16%. However, atazanavir levels still remains high enough to prevent HIV virus replication. Therefore, the decrease in ritonavir levels is not likely to be clinically significant.
Tetracycline Antibiotics
Zinc might reduce levels of tetracycline antibiotics.
Tetracyclines form complexes with zinc in the gastrointestinal tract, which can reduce absorption of both the tetracycline and zinc when taken at the same time. Taking zinc sulfate 200 mg with tetracycline reduces absorption of the antibiotic by 30% to 40%. Demeclocycline and minocycline cause a similar interaction. However, doxycycline does not seem to interact significantly with zinc. Advise patients to take tetracyclines at least 2 hours before, or 4-6 hours after, zinc supplements to avoid any interactions.
Amiloride (Midamor)
Amiloride can modestly reduce zinc excretion and increase zinc levels.
Clinical research shows that amiloride can reduce urinary zinc excretion, especially at doses of 10 mg per day or more. This zinc-sparing effect can help to counteract zinc losses caused by thiazide diuretics, but it is unlikely to cause zinc toxicity at usual amiloride doses. The other potassium-sparing diuretics, spironolactone (Aldactone) and triamterene (Dyrenium), do not seem to have a zinc-sparing effect.
Atazanavir (Reyataz)
Zinc modestly reduces levels of atazanavir, although this effect does not seem to be clinically significant.
Clinical research shows that zinc might decrease serum atazanavir levels by chelating with atazanavir in the gut and preventing its absorption. Although a single dose of zinc sulfate (Solvazinc tablets) 125 mg orally does not affect atazanavir concentrations in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate 125 mg daily for 2 weeks reduces plasma levels of atazanavir by about 22% in these patients. However, despite this decrease, atazanavir levels still remain at high enough concentrations for the prevention of HIV virus replication.
Vitamin B12
Metformin (Glucophage)
Metformin, a common medication used to manage type 2 diabetes, has been associated with lower vitamin B12 levels in some individuals. Prolonged use of metformin can interfere with the absorption of B12 in the digestive system, potentially leading to a deficiency in this essential vitamin.
Vitamin K2
Warfarin (Coumadin)
Vitamin K can antagonize and reverse the therapeutic effects of warfarin.
Vitamin K antagonizes the effects of warfarin. Excessive vitamin K intake, either from supplements or from changes in the diet, can reduce the anticoagulant effect of warfarin.
Brand information
Manufacturer and brand details for Essential for Men, from the product label.
Essential for Men by Ritual: Common Questions
Does Essential for Men by Ritual interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Does this product work for general men's health?
Is it safe to take this if I'm on metformin for diabetes?
Can I take this with my blood thinner?
What are the most common side effects?
Is this safe during pregnancy?
Can I take this while breastfeeding?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Essential for Men is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Essential for Men’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin B12
Interacts with 20 drugsVitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very helpful for people who are deficient — su...
Read the full Vitamin B12 monograph → Herb & supplement monographVitamin K
Interacts with 2 drugsVitamin K is an essential nutrient your body needs for normal blood clotting and to support healthy bones. Most people get enough from food, but supplements are sometimes used for deficiency...
Read the full Vitamin K monograph → Herb & supplement monographVitamin A
Interacts with 387 drugsVitamin A is an essential nutrient important for vision, skin, immune function, and growth. Most people get enough from a balanced diet, and supplements are mainly useful for correcting a tr...
Read the full Vitamin A monograph → Herb & supplement monographBoron
Boron is a trace mineral found in many plant foods and sold as a supplement, mainly promoted for bone, joint, and hormone health. The human evidence for most of these uses is limited or prel...
Read the full Boron monograph → Herb & supplement monographMagnesium
Interacts with 295 drugsMagnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preventing or correcting deficiency. Some othe...
Read the full Magnesium monograph → Herb & supplement monographZinc
Interacts with 67 drugsZinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but supplements can help correct or prevent a defici...
Read the full Zinc monograph → Herb & supplement monographVitamin D
Interacts with 715 drugsVitamin D is a fat-soluble vitamin that helps your body absorb calcium and is important for healthy bones, muscles, and immune function. Many people, especially those with low sun exposure,...
Read the full Vitamin D monograph → Herb & supplement monographVitamin E
Interacts with 764 drugsVitamin E is an essential fat-soluble vitamin and antioxidant that most people get in adequate amounts from a normal diet. Supplements can help correct a true deficiency, but high-dose vitam...
Read the full Vitamin E monograph → Herb & supplement monographDocosahexaenoic Acid (dha)
Interacts with 375 drugsDHA is an omega-3 fatty acid found in fatty fish and algae that is a building block for the brain, nervous system, and eyes. It is widely used and generally well tolerated, with the stronges...
Read the full Docosahexaenoic Acid (dha) monograph →Sources & How We Checked
Essential for Men's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 387 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Vitamin B12 30 references
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Hartman TJ, Woodson K, Stolzenberg-Solomon R, et al. Association of the B-vitamins pyridoxal 5'-phosphate (B6), B12, and folate with lung cancer risk in older men. Am J Epidemiol 2001;153:688-94.. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Lange H, Suryapranata H, De Luca G, et al. Folate therapy and in-stent restenosis after coronary stenting. N Engl J Med 2004;350:2673-81. PubMed
- Collin, S. M., Metcalfe, C., Refsum, H., Lewis, S. J., Zuccolo, L., Smith, G. D., Chen, L., Harris, R., Davis, M., Marsden, G., Johnston, C., Lane, J. A., Ebbing, M., Bonaa, K. H., Nygard, O., Ueland, P. M., Grau, M. V., Baron, J. A., Donovan, J. L., Nea
- Geissbuhler, P., Mermillod, B., and Rapin, C. H. Elevated serum vitamin B12 levels associated with CRP as a predictive factor of mortality in palliative care cancer patients: a prospective study over five years. J.Pain Symptom.Manage. 2000;20(2):93-103. PubMed
- Salles, N., Herrmann, F., Sakbani, K., Rapin, C. H., and Sieber, C. High vitamin B12 level: a strong predictor of mortality in elderly inpatients. J Am Geriatr.Soc 2005;53(5):917-918.
- Looker, H. C., Fagot-Campagna, A., Gunter, E. W., Pfeiffer, C. M., Sievers, M. L., Bennett, P. H., Nelson, R. G., Hanson, R. L., and Knowler, W. C. Homocysteine and vitamin B(12) concentrations and mortality rates in type 2 diabetes. Diabetes Metab Res R
- Uhl, W., Nolting, A., Golor, G., Rost, K. L., and Kovar, A. Safety of hydroxocobalamin in healthy volunteers in a randomized, placebo-controlled study. Clin Toxicol (Phila) 2006;44 Suppl 1:17-28. PubMed
- Borron, S. W., Baud, F. J., Barriot, P., Imbert, M., and Bismuth, C. Prospective study of hydroxocobalamin for acute cyanide poisoning in smoke inhalation. Ann Emerg.Med 2007;49(6):794-801, 801. PubMed
- Borron, S. W., Baud, F. J., Megarbane, B., and Bismuth, C. Hydroxocobalamin for severe acute cyanide poisoning by ingestion or inhalation. Am J Emerg.Med 2007;25(5):551-558. PubMed
- Lewis, J. G. Gout, Steatorrhoea, and Megaloblastic Anaemia. Ann Rheum.Dis 1962;21(3):284-286. PubMed
- Tal, S., Shavit, Y., Stern, F., and Malnick, S. Association between vitamin B12 levels and mortality in hospitalized older adults. J Am Geriatr.Soc 2010;58(3):523-526. PubMed
- Baztan, J. J., Gavidia, J. J., Gomez-Pavon, J., Esteve, A., and Ruiperez, I. High vitamin B12 levels and in-hospital mortality. J Am Geriatr.Soc 2010;58(11):2237-2238. PubMed
- Omboni, E., Checchini, M., and Longoni, F. [Hypopotassemia and megaloblastic anemia. Presentation of a case]. Minerva Med 8-31-1987;78(16):1255-1257.
- Aalfs As, Scholvinck LH, Horvath B. Acneiform eruption in a 5-year old due to vitamin B12 supplementation. Eur J Dermatol 2013;23(5):726-7. PubMed
- Balta I, Ozuguz P. Vitamin B12-induced acneiform eruption. Cutan Ocul Toxicol 2014;33(2):94-5. PubMed
- Carman KB, Belgemen T, Yis U. Involuntary movements misdiagnosed as seizure during vitamin B12 treatment. Pediatr Emerg Care 2013;29(11):1223-4. PubMed
- Djuric V, Bogic M, Popadic AP, et al. Anaphylactic reaction to hydroxycobalamin with tolerance to cyanocobalamin. Ann Allergy Asthma Immunol 2012;108(3):207-8. PubMed
- Kartel O, Gulec M, Demirel F, et al. Vitamin B12 allergy and successful desensitization with cyanocobalamin: A case report. Allergol Immunopath (Madr) 2012;40(5):324-5.
- Patiroglu T, Unal E, Yildirim S. Infantile tremor syndrome associated with cobalamin therapy: A case report. Clin Neurol Neurosurg 2013;115(9):1903-5. PubMed
- Schulte S, Barkema LW, Kardaun SH. Long-lasting atypical acneiform eruption with prominent comedones induced by hydroxocobalamin (vitamin B12). J Dtsch Dermatol Ges 2014;12(6):502-3.
- Zanus C, Alberini E, Costa P, et al. Involuntary movements after correction of vitamin B12 deficiency: A video-case report. Epileptic Disord 2012;14(2):174-80. PubMed
- Fanidi A, Carreras-Torres R, Larose TL, et al. Is high vitamin B12 status a cause of lung cancer? Int J Cancer. 2019 Sep 15;145(6):1499-1503. PubMed
- Fujita Y, Mizukami T, Maya Y, et al. Vitamin B12 allergy manifesting as lymphomatoid contact dermatitis. Eur J Dermatol. 2020;30(3):304-305. PubMed
- Dépret F, Hoffmann C, Daoud L, et al. Association between hydroxocobalamin administration and acute kidney injury after smoke inhalation: a multicenter retrospective study. Crit Care. 2019;23(1):421. PubMed
- Khairan P, Sobue T, Eshak ES, et al. Association of dietary intakes of vitamin B12, vitamin B6, folate, and methionine with the risk of esophageal cancer: the Japan Public Health Center-based (JPHC) prospective study. BMC Cancer 2021;21(1):982. PubMed
- Evans J, Pandya A, Ding Y, Qunibi WY. Hydroxocobalamin-Induced Oxalate Nephropathy in a Patient With Smoke Inhalation. Kidney Int Rep 2021;6(8):2228-2231. PubMed
- Lacombe V, Chabrun F, Lacout C, et al. Persistent elevation of plasma vitamin B12 is strongly associated with solid cancer. Sci Rep 2021;11(1):13361. PubMed
- Pegalajar-García MD, Cebolla-Verdugo M, Prados-Carmona Á, Llamas-Segura C, Navarro-Triviño FJ. Systemic allergic dermatitis to cobalt present in cyanocobalamin supplementation. Contact Dermatitis 2023;89(3):203-205. PubMed
Vitamin K 11 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Crowther MA, Ageno W, Garcia D, et al. Oral vitamin K versus placebo to correct excessive anticoagulation in patients receiving warfarin: a randomized trial. Ann Intern Med. 2009;150(5):293-300. PubMed
- Dietary vitamin K guidance: an effective strategy for stable control of oral anticoagulation? Nutr Rev. 2010;68(3):178-81. PubMed
- Kim JS, Nafziger AN, Gaedigk A, et al. Effects of oral vitamin K on S- and R-warfarin pharmacokinetics and pharmacodynamics: enhanced safety of warfarin as a CYP2C9 probe. J Clin Pharmacol. 2001 Jul;41(7):715-22. PubMed
- Riegert-Johnson, D. L. and Volcheck, G. W. The incidence of anaphylaxis following intravenous phytonadione (vitamin K1): a 5-year retrospective review. Ann.Allergy Asthma Immunol. 2002;89(4):400-406. PubMed
- Dezee, K. J., Shimeall, W. T., Douglas, K. M., Shumway, N. M., and O'malley, P. G. Treatment of excessive anticoagulation with phytonadione (vitamin K): a meta-analysis. Arch.Intern.Med. 2-27-2006;166(4):391-397. DOI
- Dentali, F., Ageno, W., and Crowther, M. Treatment of coumarin-associated coagulopathy: a systematic review and proposed treatment algorithms. J.Thromb.Haemost. 2006;4(9):1853-1863. PubMed
- Caluwé R, Vandecasteele S, Van Vlem B, Vermeer C, De Vriese AS. Vitamin K2 supplementation in haemodialysis patients: a randomized dose-finding study. Nephrol Dial Transplant. 2014;29(7):1385-90.
- Huang ZB, Wan SL, Lu YJ, Ning L, Liu C, Fan SW. Does vitamin K2 play a role in the prevention and treatment of osteoporosis for postmenopausal women: a meta-analysis of randomized controlled trials. Osteoporos Int. 2015;26(3):1175-86. PubMed
- Hunnali CR, Devi U, Kitchanan S, Sethuraman G. Three Different Regimens for Vitamin K Birth Prophylaxis in Infants Born Preterm: A Randomized Clinical Trial. J Pediatr 2023;255:98-104. PubMed
Vitamin A 31 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Griffiths JK. The vitamin A paradox. J Pediatr 2000;137:604-7.. PubMed
- Hardman JG, Limbird LL, Molinoff PB, eds. Goodman and Gillman's The Pharmacological Basis of Therapeutics, 9th ed. New York, NY: McGraw-Hill, 1996.
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- FDA Talk Paper. Vitamin A and birth defects (T95-56). Food and Drug Administration, U.S. Department of Health and Human Services, Rockville, MD. October 6, 1995.
- Russell RM. The vitamin A spectrum: from deficiency to toxicity. Am J Clin Nutr 2000;71:878-84. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Feskanich D, Singh V, Willett WC, Colditz GA. Vitamin A intake and hip fractures among postmenopausal women. JAMA 2002;287:47-54. PubMed
- Melhus H, Michaelsson K, Kindmark A, et al. Excessive dietary intake of vitamin A is associated with reduced bone mineral density and increased risk for hip fracture. Ann Intern Med 1998;129:770-8. PubMed
- Michaelsson K, Lithell H, Vessby B, Melhus H. Serum retinol levels and the risk of fracture. N Engl J Med 2003;348:287-94.. PubMed
- Botterweck AA, van den Brandt PA, Goldbohm RA. Vitamins, carotenoids, dietary fiber, and the risk of gastric carcinoma: results from a prospective study after 6.3 years of follow-up. Cancer 2000;88:737-48.. DOI
- Meyskens FL Jr, Graham V, Chvapil M, et al. A phase I trial of beta-all-trans-retinoic acid delivered via a collagen sponge and a cervical cap for mild or moderate intraepithelial cervical neoplasia. J Natl Cancer Inst 1983;71:921-5..
- Hathcock JN, Hattan DG, Jenkins MY, et al. Evaluation of vitamin A toxicity. Am J Clin Nutr 1990;52:183-202.. PubMed
- Walters BN, Gubbay SS. Tetracycline and benign intracranial hypertension: report of five cases. Br Med J 1981;282:19-20.. PubMed
- Pearson MG, Littlewood SM, Bowden AN. Tetracycline and benign intracranial hypertension (letter). Br Med J 1981;282:568-9.. PubMed
- Azais-Braesco V, Pascal G. Vitamin A in pregnancy: requirements and safety limits. Am J Clin Nutr 2000;71:1325S-33S. PubMed
- Smedts HP, de Vries JH, Rakhshandehroo M, et al. High maternal vitamin E intake by diet or supplements is associated with congenital heart defects in the offspring. BJOG 2009;116:416-23. PubMed
- Grotto, I., Mimouni, M., Gdalevich, M., and Mimouni, D. Vitamin A supplementation and childhood morbidity from diarrhea and respiratory infections: a meta-analysis. J Pediatr 2003;142(3):297-304. PubMed
- Mahalanabis, D., Lahiri, M., Paul, D., Gupta, S., Gupta, A., Wahed, M. A., and Khaled, M. A. Randomized, double-blind, placebo-controlled clinical trial of the efficacy of treatment with zinc or vitamin A in infants and young children with severe acute l
- Long, K. Z., Montoya, Y., Hertzmark, E., Santos, J. I., and Rosado, J. L. A double-blind, randomized, clinical trial of the effect of vitamin A and zinc supplementation on diarrheal disease and respiratory tract infections in children in Mexico City, Mex
- Fritz, H., Kennedy, D., Fergusson, D., Fernandes, R., Doucette, S., Cooley, K., Seely, A., Sagar, S., Wong, R., and Seely, D. Vitamin A and retinoid derivatives for lung cancer: a systematic review and meta analysis. PLoS.One. 2011;6(6):e21107. PubMed
- Mayo-Wilson, E., Imdad, A., Herzer, K., Yakoob, M. Y., and Bhutta, Z. A. Vitamin A supplements for preventing mortality, illness, and blindness in children aged under 5: systematic review and meta-analysis. BMJ 2011;343:d5094. PubMed
- Mazumder S, Taneja S, Bhatia K, Yoshida S, Kaur J, Dube B, Toteja GS, Bahl R, Fontaine O, Martines J, Bhandari N; Neovita India Study Group. Efficacy of early neonatal supplementation with vitamin A to reduce mortality in infancy in Haryana, India (Neovit
- Baineni R, Gulati R, Delhi CK. Vitamin A toxicity presenting as bone pain. Arch Dis Child. 2017;102(6):556-8. PubMed
- Darlow BA, Graham PJ, Rojas-Reyes MX. Vitamin A supplementation to prevent mortality and short- and long-term morbidity in very low birth weight infants. Cochrane Database Syst Rev. 2016;(8):CD000501. PubMed
- Haider BA, Sharma R, Bhutta ZA. Neonatal vitamin A supplementation for the prevention of mortality and morbidity in term neonates in low and middle income countries. Cochrane Database Syst Rev. 2017;2:CD006980. PubMed
- Mohammad YM, Raslan IR, Al-Hussain FA. Idiopathic Intracranial Hypertension Induced by Topical Application of Vitamin A. J Neuroophthalmol. 2016;36(4):412-3. PubMed
- Masnadi Shirazi K, Nikniaz Z, Masnadi Shirazi A, Rohani M. Vitamin A supplementation decreases disease activity index in patients with ulcerative colitis: A randomized controlled clinical trial. Complement Ther Med. 2018 Dec;41:215-219. PubMed
- Ding Y, Hu P, Yang Y, et al. Impact of maternal daily oral low-dose vitamin A supplementation on the mother-infant pair: a randomised placebo-controlled trial in China. Nutrients 2021;13(7):2370. PubMed
- Knapik JJ, Hoedebecke SS. Vitamin A and bone fractures: systematic review and meta-analysis. J Spec Oper Med 2021;21(2):100-7. PubMed
- Imdad A, Mayo-Wilson E, Haykal MR, et al. Vitamin A supplementation for preventing morbidity and mortality in children from six months to five years of age. Cochrane Database Syst Rev 2022;3(3):CD008524. PubMed
Boron 6 references
- Ellenhorn MJ, et al. Ellenhorn's Medical Toxicology: Diagnoses and Treatment of Human Poisoning. 2nd ed. Baltimore, MD: Williams & Wilkins, 1997.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Thai L, Hart LL. Boric acid vaginal suppositories. Ann Pharmacother 1993;27:1355-7.
- Acs N, Banhidy F, Puho E, Czeizel AE. Teratogenic effects of vaginal boric acid treatment during pregnancy. Int J Gynaecol Obstet 2006;93:55-6. PubMed
- Garabrant, D. H., Bernstein, L., Peters, J. M., and Smith, T. J. Respiratory and eye irritation from boron oxide and boric acid dusts. J Occup Med 1984;26(8):584-586. PubMed
- Hjelm C, Harari F, Vahter M. Pre- and postnatal environmental boron exposure and infant growth: results from a mother-child cohort in northern Argentina. Environ Res 2019;171:60-8. PubMed
Magnesium 82 references
- Rodin SM, Johnson BF. Pharmacokinetic interactions with digoxin. Clin Pharmacokinet 1988;15:227-44.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Dahle LO, Berg G, Hammar M, et al. The effect of oral magnesium substitution on pregnancy-induced leg cramps. Am J Obstet Gynecol 1995;173:175-80. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Peikert A, Wilimzig C, Kohne-Volland R. Prophylaxis of migraine with oral magnesium: results from a prospective, multi-center, placebo-controlled and double-blind randomized study. Cephalalgia 1996;16:257-63. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Washington, DC: National Academy Press, 1999. Available at: http://books.nap.edu/books/0309063507/html/index.html.
- Birrer RB, Shallash AJ, Totten V. Hypermagnesemia-induced fatality following epsom salt gargles. J Emerg Med 2002;22:185-8. PubMed
- Ryan MP. Diuretics and potassium/magnesium depletion. Directions for treatment. Am J Med 1987;82:38-47.. PubMed
- Hollifield JW. Magnesium depletion, diuretics, and arrhythmias. Am J Med 1987;82:30-7.. PubMed
- Heidenreich O. Mode of action of conventional and potassium-sparing diuretics--aspects with relevance to Mg-sparing effects. Magnesium 1984;3:248-56..
- Pfaffenrath V, Wessely P, Meyer C, et al. Magnesium in the prophylaxis of migraine--a double-blind placebo-controlled study. Cephalalgia 1996;16:436-40.. PubMed
- Wang F, Van Den Eeden SK, Ackerson LM, et al. Oral magnesium oxide prophylaxis of frequent migrainous headache in children: a randomized, double-blind, placebo-controlled trial. Headache 2003;43:601-10.. PubMed
- Sompolinsky D, Samra Z. Influence of magnesium and manganese on some biological and physical properties of tetracycline. J Bacteriol 1972;110:468-76.. PubMed
- Jeyabalan A, Caritis SN. Pharmacologic inhibition of preterm labor. Clin Obstet Gynecol 2002;45:99-113. PubMed
- Mittendorf R, Dambrosia J, Pryde PG, et al. Association between the use of antenatal magnesium sulfate in preterm labor and adverse health outcomes in infants. Am J Obstet Gynecol 2002;186:1111-8.. PubMed
- Witlin AG, Sibai BM. Magnesium sulfate therapy in preeclampsia and eclampsia. Obstet Gynecol 1998;92:883-9.. DOI
- Crowther CA, Hiller JE, Doyle LW. Magnesium sulphate for preventing preterm birth in threatened preterm labour. Cochrane Database Syst Rev 2002;4:CD001060. . PubMed
- Davey MJ, Teubner D. A randomized controlled trial of magnesium sulfate, in addition to usual care, for rate control in atrial fibrillation. Ann Emerg Med 2005;45:347-53.. PubMed
- L'Hommedieu CS, Nicholas D, Armes DA, et al. Potentiation of magnesium sulfate--induced neuromuscular weakness by gentamicin, tobramycin, and amikacin. J Pediatr 1983;102:629-31..
- Dunn CJ, Goa KL. Risedronate: a review of its pharmacological properties and clinical use in resorptive bone disease. Drugs 2001;61:685-712..
- Kass L, Weekes J, Carpenter L. Effect of magnesium supplementation on blood pressure: a meta-analysis. Eur J Clin Nutr 2012;66:411-8. PubMed
- Koontz SL, Friedman SA, Schwartz ML. Symptomatic hypocalcemia after tocolytic therapy with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 2004;190(6):1773-6. PubMed
- Snyder SW, Cardwell MS. Neuromuscular blockade with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 1989;161(1):35-6. PubMed
- Waisman GD, Mayorga LM, Cámera MI, et al. Magnesium plus nifedipine: potentiation of hypotensive effect in preeclampsia? Am J Obstet Gynecol. 1988;159(2):308-9. PubMed
- Brown DD, Juhl RP. Decreased bioavailability of digoxin due to antacids and kaolin-pectin. N Engl J Med. 1976;295(19):1034-7. PubMed
- Allen MD, Greenblatt DJ, Harmatz JS, et al. Effect of magnesium--aluminum hydroxide and kaolin--pectin on absorption of digoxin from tablets and capsules. J Clin Pharmacol. 1981;21(1):26-30. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an in vitro study. Thromb Haemost. 1996;76(1):88-93. DOI
- Ravn HB, Kristensen SD, Vissinger H, et al. Magnesium inhibits human platelets. Blood Coagul Fibrinolysis. 1996;7(2):241-4. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an infusion study in healthy volunteers. Thromb Haemost. 1996;75(6):939-44. DOI
- Neuvonen PJ, Kivistö KT. The effects of magnesium hydroxide on the absorption and efficacy of two glibenclamide preparations. Br J Clin Pharmacol. 1991;32(2):215-20. PubMed
- Kivistö KT, Neuvonen PJ. Enhancement of absorption and effect of glipizide by magnesium hydroxide. Clin Pharmacol Ther. 1991;49(1):39-43. PubMed
- Neuvonen PJ, Kivistö KT. Enhancement of drug absorption by antacids. An unrecognised drug interaction. Clin Pharmacokinet. 1994;27(2):120-8. PubMed
- Shechter, M., Merz, C. N., Paul-Labrador, M., Meisel, S. R., Rude, R. K., Molloy, M. D., Dwyer, J. H., Shah, P. K., and Kaul, S. Beneficial antithrombotic effects of the association of pharmacological oral magnesium therapy with aspirin in coronary heart
- Ganzevoort, J. W., Hoogerwaard, E. M., and van der Post, J. A. [Hypocalcemic delirium due to magnesium sulphate therapy in a pregnant woman with pre-eclampsia]. Ned.Tijdschr.Geneeskd. 8-3-2002;146(31):1453-1456.
- Horner, S. M. Efficacy of intravenous magnesium in acute myocardial infarction in reducing arrhythmias and mortality. Meta-analysis of magnesium in acute myocardial infarction. Circulation 1992;86(3):774-779. PubMed
- Azria, E., Tsatsaris, V., Goffinet, F., Kayem, G., Mignon, A., and Cabrol, D. [Magnesium sulfate in obstetrics: current data]. J Gynecol.Obstet.Biol.Reprod.(Paris) 2004;33(6 Pt 1):510-517.
- Magee, L. A., Miremadi, S., Li, J., Cheng, C., Ensom, M. H., Carleton, B., Cote, A. M., and von Dadelszen, P. Therapy with both magnesium sulfate and nifedipine does not increase the risk of serious magnesium-related maternal side effects in women with p
- Henyan, N. N., Gillespie, E. L., White, C. M., Kluger, J., and Coleman, C. I. Impact of intravenous magnesium on post-cardiothoracic surgery atrial fibrillation and length of hospital stay: a meta-analysis. Ann.Thorac.Surg. 2005;80(6):2402-2406. PubMed
- Li, J., Zhang, Q., Zhang, M., and Egger, M. Intravenous magnesium for acute myocardial infarction. Cochrane.Database.Syst.Rev. 2007;(2):CD002755. PubMed
- Doyle, L. W., Crowther, C. A., Middleton, P., Marret, S., and Rouse, D. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane.Database.Syst.Rev. 2009;(1):CD004661. PubMed
- Han, S., Crowther, C. A., and Moore, V. Magnesium maintenance therapy for preventing preterm birth after threatened preterm labour. Cochrane.Database.Syst.Rev. 2010;(7):CD000940. PubMed
- Duley, L., Gulmezoglu, A. M., Henderson-Smart, D. J., and Chou, D. Magnesium sulphate and other anticonvulsants for women with pre-eclampsia. Cochrane.Database.Syst.Rev. 2010;(11):CD000025. PubMed
- Conde-Agudelo, A., Romero, R., and Kusanovic, J. P. Nifedipine in the management of preterm labor: a systematic review and metaanalysis. Am J Obstet.Gynecol. 2011;204(2):134-20. PubMed
- Wong, G. K., Boet, R., Poon, W. S., Chan, M. T., Gin, T., Ng, S. C., and Zee, B. C. Intravenous magnesium sulphate for aneurysmal subarachnoid hemorrhage: an updated systemic review and meta-analysis. Crit Care 2011;15(1):R52. PubMed
- Magee, L., Sawchuck, D., Synnes, A., and von, Dadelszen P. SOGC Clinical Practice Guideline. Magnesium sulphate for fetal neuroprotection. J Obstet.Gynaecol.Can. 2011;33(5):516-529.
- Doyle, L. W. Antenatal magnesium sulfate and neuroprotection. Curr Opin Pediatr 2012;24(2):154-159. PubMed
- McDonald, S. D., Lutsiv, O., Dzaja, N., and Duley, L. A systematic review of maternal and infant outcomes following magnesium sulfate for pre-eclampsia/eclampsia in real-world use. Int J Gynaecol.Obstet. 2012;118(2):90-96. PubMed
- Gordon, M., Naidoo, K., Akobeng, A. K., and Thomas, A. G. Osmotic and stimulant laxatives for the management of childhood constipation. Cochrane.Database.Syst.Rev. 2012;7:CD009118. PubMed
- Dodd, J. M., Crowther, C. A., and Middleton, P. Oral betamimetics for maintenance therapy after threatened preterm labour. Cochrane.Database.Syst.Rev. 2012;12:CD003927. PubMed
- Wu, X., Wang, C., Zhu, J., Zhang, C., Zhang, Y., and Gao, Y. Meta-analysis of randomized controlled trials on magnesium in addition to beta-blocker for prevention of postoperative atrial arrhythmias after coronary artery bypass grafting. BMC.Cardiovasc.D PubMed
- Thorp, J. M., Jr., Katz, V. L., Campbell, D., and Cefalo, R. C. Hypersensitivity to magnesium sulfate. Am.J.Obstet.Gynecol. 1989;161(4):889-890. PubMed
- Duley L and Gulmezoglu AM. Magnesium sulphate versus lytic cocktail for eclampsia. Cochrane Database of Systematic Reviews 2000;(3) PubMed
- Gibbins KJ, Browning KR, Lopes VV, Anderson BL, Rouse DJ. Evaluation of the clinical use of magnesium sulfate for cerebral palsy prevention. Obstet Gynecol 2013;121(2 Pt 1):235-40. PubMed
- Ji D. Oral magnesium sulfate causes perforation during bowel preparation for fiberoptic colonoscopy in patients with colorectal cancer. J Emerg Med 2012;43(4):716-7. PubMed
- Yagi T, Naito T, Mino Y, Umemura K, Kawakami J. Impact of concomitant antacid administration on gabapentin plasma exposure and oral bioavailability in healthy adult subjects. Drug Metab Pharmacokinet 2012;27(2):248-54. PubMed
- Yamasaki M, Funakoshi S, Matsuda S, Imazu T, Takeda Y, Murakami T, Maeda Y. Interaction of magnesium oxide with gastric acid secretion inhibitors in clinical pharmacotherapy. Eur J Clin Pharmacol 2014;70(8):921-4. PubMed
- Choi ES, Jeong WJ, Ahn SH, Oh AY, Jeon YT, Do SH. Magnesium sulfate accelerates the onset of low-dose rocuronium in patients undergoing laryngeal microsurgery. J Clin Anesth. 2017 Feb;36:102-106. PubMed
- Ikee R, Toyoyama T, Endo T, Tsunoda M, Hashimoto N. Impact of sevelamer hydrochloride on serum magnesium concentrations in hemodialysis patients. Magnes Res. 2016 Apr 1;29(4):184-90. PubMed
- Miller ES, Sakowicz A, Leger E. Lange E, Yee LM. The association between receipt of intrapartum magnesium and postpartum hemorrhage. Am J Obstet Gynecol 2018;218(1 Suppl):S165.
- Rodríguez-Rubio L, Solis Garcia Del Pozo J, Nava E, Jordán J. Interaction between magnesium sulfate and neuromuscular blockers during the perioperative period. A systematic review and meta-analysis. J Clin Anesth. 2016;34:524-34. PubMed
- Brown RS. Magnesium Sulfate: Another Cause of a Solute Diuresis. Am J Kidney Dis. 2017;69(4):550-551. PubMed
- Park H, Qin R, Smith TJ, et al. North Central Cancer Treatment Group N10C2 (Alliance): a double-blind placebo-controlled study of magnesium supplements to reduce menopausal hot flashes. Menopause. 2015;22(6):627-32. PubMed
- Sakanoue M, Sanada J, Kanekura T. Skin eruption elicited by magnesium oxide (Maglax). J Dermatol. 2016;43(2):221-2.
- Iwamuro M, Saito S, Yoshioka M, et al. A Magnesium Oxide Bezoar. Intern Med. 2018;57(21):3087-3091. PubMed
- Vilchez G, Dai J, Kumar K, Mundy D, Kontopoulos E, Sokol RJ. Racial/ethnic disparities in magnesium sulfate neuroprotection: a subgroup analysis of a multicenter randomized controlled trial. J Matern Fetal Neonatal Med. 2018;31(17):2304-2311. PubMed
- Drug Safety Communication: FDA Recommends Against Prolonged Use of Magnesium Sulfate to Stop Pre-term Labor Due to Bone Changes in Exposed Babies. U.S. Food and Drug Administration (FDA), May 30, 2013. https://www.fda.gov/downloads/Drugs/DrugSafety/UCM353
- Committee Opinion: Magnesium Sulfate Use in Obstetrics. The American College of Obstetricians and Gynecologists Committee on Obstetric Practice Society for Maternal-Fetal Medicine, Number 652, January 2016. https://www.acog.org/Clinical-Guidance-and-Publi
- Kashihara Y, Terao Y, Yoda K, et al. Effects of magnesium oxide on pharmacokinetics of L-dopa/carbidopa and assessment of pharmacodynamic changes by a model-based simulation. Eur J Clin Pharmacol. 2019;75(3):351-361. PubMed
- Shepherd E, Salam RA, Manhas D, et al. Antenatal magnesium sulphate and adverse neonatal outcomes: A systematic review and meta-analysis. PLoS Med. 2019;16(12):e1002988. PubMed
- Hong JY, Hong JY, Choi YS, et al. Antenatal magnesium sulfate treatment and risk of necrotizing enterocolitis in preterm infants born at less than 32 weeks of gestation. Sci Rep. 2020;10(1):12826. PubMed
- Schuh S, Sweeney J, Rumantir M, et al. Effect of nebulized magnesium vs placebo added to albuterol on hospitalization among children with refractory acute asthma treated in the emergency department: a randomized clinical trial. JAMA. 2020;324(20):2038-20 PubMed
- Almeida CED, Carvalho LR, Andrade CVC, Nascimento PD Jr, Barros GAM, Modolo NSP. Effects of magnesium sulphate on the onset time of rocuronium at different doses: a randomized clinical trial. Braz J Anesthesiol. 2021;71(5):482-8. PubMed
- Gochi Valdovinos A, Arriaga-Redondo M, Dejuan Bitriá E, Pérez Rodríguez I, Márquez Isidro E, Blanco Bravo D. Prenatal therapy with magnesium sulphate and intestinal obstruction due to meconium in preterm newborns. An Pediatr (Engl Ed). 2022 Feb;96(2):138- PubMed
- Iio K, Kondo E, Shibata E, et al. Long-term tocolysis with magnesium sulfate as a risk factor for low bone mass: a case series. J Med Cases. 2022 Feb;13(2):47-50. PubMed
- Eiraku K, Uozumi Y, Hieda M, Maruyama T, Nomura H. A senile case of heart failure associated with hypermagnesemia induced by magnesium-containing laxative agent. Geriatr Gerontol Int. 2022;22(10):897-899.
- Enayati A, Gin JH, Sajeev JK, et al. Efficacy of intravenous magnesium for the management of non-post operative atrial fibrillation with rapid ventricular response: A systematic review and meta-analysis. J Cardiovasc Electrophysiol 2023;34(5):1286-1295. PubMed
- Su YH, Luo DC, Pang Y. Effects of intraoperative Magnesium sulfate infusion on emergency agitation during general anesthesia in patients undergoing radical mastectomy: a randomized controlled study. BMC Anesthesiol 2023;23(1):326. PubMed
- Han J, Park HY, Shin HJ, Chung SH, Do SH. Effects of magnesium sulphate on neostigmine-induced recovery from moderate neuromuscular blockade with rocuronium: a randomized controlled trial. Magnes Res 2023;36(2):31-39. PubMed
- Lee AT, Cordova JC, Jamplis RP, Pomicter GR. Posterior Reversible Encephalopathy Syndrome and Eclampsia in the Setting of Magnesium Toxicity: A Case Report. A A Pract 2023;17(11):e01726. PubMed
- Darmawan D, Rengganis I, Rumende CM, et al. Effectiveness and Safety of Nebulized Magnesium as Last Line Treatment in Adults with Acute Asthma Attack: A Systematic Review and Meta-Analysis. Acta Med Indones 2024;56(1):3-12.
- Shepherd ES, Goldsmith S, Doyle LW, et al. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane Database Syst Rev 2024;5(5):CD004661. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Zinc 88 references
- Barceloux DG. Zinc. J Toxicol Clin Toxicol 1999;37:279-92.
- Eby GA, Davis DR, Halcomb WW. Reduction in duration of common colds by zinc gluconate lozenges in a double-blind study. Antimicrob Agents Chemother 1984;25:20-4. DOI
- Smith DS, Helzner EC, Nuttall CE Jr, et al. Failure of zinc gluconate in treatment of acute upper respiratory tract infections. Antimicrob Agents Chemother 1989;33:646-8. PubMed
- Blondeau JM. Expanded activity and utility of the new fluoroquinolones: a review. Clin Ther 1999;21:3-40. PubMed
- Reyes AJ, Olhaberry JV, Leary WP, et al. Urinary zinc excretion, diuretics, zinc deficiency and some side-effects of diuretics. S Afr Med J 1983;64:936-41.
- Kugelmas M. Preliminary observation: oral zinc sulfate replacement is effective in treating muscle cramps in cirrhotic patients. J Am Coll Nutr 2000;19:13-5. PubMed
- Hebel SK, ed. Drug Facts and Comparisons. 52nd ed. St. Louis: Facts and Comparisons, 1998.
- Chan S, Gerson B, Subramaniam S. The role of copper, molybdenum, selenium, and zinc in nutrition and health. Clin Lab Med 1998;18:673-85. DOI
- Brewer GJ, Yuzbasiyan-Gurkan V, Johnson V, et al. Treatment of Wilson's disease with zinc: XI. Interaction with other anticopper agents. J Am Coll Nutr 1993;12:26-30. PubMed
- Fosmire GJ. Zinc toxicity. Am J Clin Nutr 1990;51:225-7.
- Lomaestro BM, Bailie GR. Absorption interactions with fluoroquinolones. 1995 update. Drug Saf 1995;12:314-33. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Seelig MS. Auto-immune complications of D-penicillamine - A possible result of zinc and magnesium depletion and of pyridoxine inactivation. J Am Coll Nutr 1982;1:207-14. PubMed
- Neuvonen PJ. Interactions with the absorption of tetracyclines. Drugs 1976;11:45-54.. PubMed
- Hirt M, Nobel S, Barron E. Zinc nasal gel for the treatment of common cold symptoms: A double-blind, placebo-controlled trial. Ear Nose Throat J 2000;79:778-82.. DOI
- Simkin PA. Oral zinc sulphate in rheumatoid arthritis. Lancet 1976;2:539-42. PubMed
- Wray D. A double-blind trial of systemic zinc sulfate in recurrent aphthous stomatitis. Oral Surg Oral Med Oral Pathol 1982;53:469-72. PubMed
- Douglas RM, Miles HB, Moore BW, et al. Failure of effervescent zinc acetate lozenges to alter the course of upper respiratory tract infections in Australian adults. Antimicrob Agents Chemother 1987;31:1263-5. PubMed
- Lagiou P, Wuu J, Trichopoulou A, et al. Diet and benign prostatic hyperplasia: a study in Greece. Urology 1999;54:284-90. PubMed
- Ewing CI, Gibbs AC, Ashcroft C, David TJ. Failure of oral zinc supplementation in atopic eczema. Eur J Clin Nutr 1991;45:507-10.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Age-Related Eye Disease Study Research Group. A randomized, placebo-controlled, clinical trial of high-dose supplementation with vitamins C and E, beta carotene, and zinc for age-related macular degeneration and vision loss. AREDS report no. 8. Arch Oph
- Greenberg JE, Lynn M, Kirsner RS, et al. Mucocutaneous pigmented macule as a result of zinc deposition. J Cutan Pathol 2002;29:613-5. PubMed
- Godfrey HR, Godfrey NJ, Godfrey JC, Riley D. A randomized clinical trial on the treatment of oral herpes with topical zinc oxide/glycine. Altern Ther Health Med 2001;7:49-56.
- Turner RB. Ineffectiveness of intranasal zinc gluconate for prevention of experimental rhinovirus colds. Clin Infect Dis 2001;33:1865-70. PubMed
- Belongia EA, Berg R, Liu K. A randomized trial of zinc nasal spray for the treatment of upper respiratory illness in adults. Am J Med 2001;111:103-8. PubMed
- Mossad SB. Effect of zincum gluconicum nasal gel on the duration and symptom severity of the common cold in otherwise healthy adults. QJM 2003;96:35-43. DOI
- Leitzmann MF, Stampfer MJ, Wu K, et al. Zinc supplement use and risk of prostate cancer. J Natl Cancer Inst 2003;95:1004-7.. PubMed
- Jafek BW, Linschoten M, Murrow BW. Zicam Induced Anosmia. American Rhinologic Society 49th Annual Fall Scientific Meeting abstract. Orlando, Florida. September 20, 2003. http://app.american-rhinologic.org/programs/2003ARSFallProgram071503.pdf (Accessed 24
- Uebayashi H, Hatanaka T, Kanemura F, Tonosaki K. Acute anosmia in the mouse: behavioral discrimination among the four basic taste substances. Physiol Behav 2001;72:291-6.. PubMed
- Barrett S. Zicam Marketers Sued. United States District Court Western District of Michigan Southern Division, Filed October 14, 2003, Case No. 4:03CV0146.
- Bilici M, Yildirim F, Kandil S, et al. Double-blind, placebo-controlled study of zinc sulfate in the treatment of attention deficit hyperactivity disorder. Prog Neuropsychopharmacol Biol Psychiatry 2004;28:181-90.. PubMed
- Polk RE, Healy DP, Sahai J, et al. Effect of ferrous sulfate and multivitamins with zinc on absorption of ciprofloxacin in normal volunteers. Antimicrob Agents Chemother 1989;33:1841-4. PubMed
- Mery C, Delrieu F, Ghozlan R, et al. Controlled trial of D-penicillamine in rheumatoid arthritis. Dose effect and the role of zinc. Scand J Rheumatol 1976;5:241-7. PubMed
- Penttila O, Hurme H, Neuvonen PJ. Effect of zinc sulfate on the absorption of tetracycline and doxycycline in man. Eur J Clin Pharmacol 1975;9:131-4.
- Kondo Y, Yamagata K, Satoh M, et al. Optimal administration schedule of cisplatin for bladder tumor with minimal induction of metallothionein. J Urol 2003;170:2467-70. PubMed
- Doz F, Berens ME, Deschepper CF, et al. Experimental basis for increasing the therapeutic index of cis-diamminedicarboxylatocyclobutaneplatinum(II) in brain tumor therapy by a high-zinc diet. Cancer Chemother Pharmacol 1992;29:219-26.
- Wester PO. Urinary zinc excretion during treatment with different diuretics. Acta Med Scand 1980;208:209-12. PubMed
- Golik A, Modai D, Weissgarten J, et al. Hydrochlorothiazide-amiloride causes excessive urinary zinc excretion. Clin Pharmacol Ther 1987;42:42-4. PubMed
- Leary WP, Reyes AJ, Van der Byl K. Urinary magnesium and zinc excretion after two different single doses of amiloride in healthy adults. Curr Ther Res 1983;34:205-16.
- McBride K, Slotnick B, Margolis FL. Does intranasal application of zinc sulfate produce anosmia in the mouse? An olfactometric and anatomical study. Chem Senses 2003;28:659-70. PubMed
- Burd GD. Morphological study of the effects of intranasal zinc sulfate irrigation on the mouse olfactory epithelium and olfactory bulb. Microsc Res Tech 1993;24:195-213. PubMed
- Ducray A, Bondier JR, Michel G, et al. Recovery following peripheral destruction of olfactory neurons in young and adult mice. Eur J Neurosci 2002;15:1907-17. PubMed
- Mayer AD, Rosenblatt JS. Peripheral olfactory deafferentation of the primary olfactory system in rats using ZnSO4 nasal spray with special reference to maternal behavior. Physiol Behav 1993;53:587-92. PubMed
- DeCook CA, Hirsch AR. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Tisdall FF, Brown A, Defries RD. Persistent anosmia following zinc sulfate nasal spraying. JPed 1938;18:60-2. DOI
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Public Health Advisory. Loss of sense of smell with intranasal cold remedies containing zinc. U.S. Food and Drug Administration, June 16, 2009. Available at: http://www.fda.gov/Drugs/DrugSafety/PublicHealthAdvisories/ucm166059.htm (Accessed 16 June 2009)
- Dooren JC. FDA warns against use of Zicam. The Wall Street Journal, June 16, 2009. Available at: http://online.wsj.com/article/SB124516778692319231.html#mod=djemHL?mg=com-wsj (Accessed 16 June 2009).
- Alexander TH, Davidson TM. Intranasal zinc and anosmia: the zinc-induced anosmia syndrome. Laryngoscope 2006;116:217-20.
- Health Canada / GlaxoSmithKline Consumer Healthcare. Association of long-term, excessive use of zinc-containing Poli-Grip products with myeloneuropathy and blood dyscrasias. February 18, 2010. Available at: http://hc-sc.gc.ca/dhp-mps/alt_formats/pdf/medef
- GlaxoSmithKline Consumer Advisory. GlaxoSmithKline (GSK) warns about a potential health risk associated with long-term, excessive use of GSK's zinc-containing denture adhesives Super Polygrip Original, Ultra Fresh and Extra Care. February 18, 2010. Availa
- Science M, Johnstone J, Roth DE, et al. Zinc for the treatment of the common cold: a systematic review and meta-analysis of randomized controlled trials. CMAJ 2012;184:E551-61. PubMed
- Castilla-Higuero, L., Romero-Gomez, M., Suarez, E., and Castro, M. Acute hepatitis after starting zinc therapy in a patient with presymptomatic Wilson's disease. Hepatology 2000;32(4 Pt 1):877. PubMed
- Sharquie, K. E., Najim, R. A., Farjou, I. B., and Al Timimi, D. J. Oral zinc sulphate in the treatment of acute cutaneous leishmaniasis. Clin.Exp.Dermatol. 2001;26(1):21-26. PubMed
- Dreno, B., Moyse, D., Alirezai, M., Amblard, P., Auffret, N., Beylot, C., Bodokh, I., Chivot, M., Daniel, F., Humbert, P., Meynadier, J., and Poli, F. Multicenter randomized comparative double-blind controlled clinical trial of the safety and efficacy of
- Moore, R. Bleeding gastric erosion after oral zinc sulphate. Br.Med J 3-25-1978;1(6115):754. PubMed
- Jafek, B. W., Linschoten, M. R., and Murrow, B. W. Anosmia after intranasal zinc gluconate use. Am J Rhinol. 2004;18(3):137-141. DOI
- Simonart, T. and de, Maertelaer, V. Systemic treatments for cutaneous warts: a systematic review. J Dermatolog.Treat. 2012;23(1):72-77. PubMed
- Cochran, R. J., Tucker, S. B., and Flannigan, S. A. Topical zinc therapy for acne vulgaris. Int.J Dermatol. 1985;24(3):188-190. DOI
- Morgan, A. A. Bleeding gastric erosion after oral zinc sulphate. Br.Med.J. 5-13-1978;1(6122):1283-1284. PubMed
- Murphy, J. V. Intoxication following ingestion of elemental zinc. JAMA 6-22-1970;212(12):2119-2120.
- Lang, C. J., Rabas-Kolominsky, P., Engelhardt, A., Kobras, G., and Konig, H. J. Fatal deterioration of Wilson's disease after institution of oral zinc therapy. Arch Neurol. 1993;50(10):1007-1008. PubMed
- Fjellner, B. Drug-induced lupus erythematosus aggravated by oral zinc therapy. Acta Derm.Venereol. 1979;59(4):368-370. DOI
- Varas Lorenzo, M. J. Zinc acexamate and ranitidine in the short- and mid-term management of gastroduodenal ulcers. Curr Ther Res 21986;39:19-29.
- Bosch, F. and Jimenez, E. Post-marketing surveillance of zinc acexamate in peptic ulcer treatment. Clin Trials J 1990;27:301-312.
- DeCook, C. A. and Hirsch, A. R. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Crown LA, May JA. Zinc toxicity: denture adhesives, bone marrow failure and polyneuropathy. Tenn Med. 2012 Feb;105(2):39-40, 42.
- Dadamio J, Van Tournout M, Teughels W, Dekeyser C, Coucke W, Quirynen M. Efficacy of different mouthrinse formulations in reducing oral malodour: a randomized clinical trial. J Clin Periodontol. 2013 May;40(5):505-13. PubMed
- Moyle G, Else L, Jackson A, Back D, Yapa MH, Seymour N, Ringner-Nackter L, Karolia Z, Gazzard B, Boffito M. Coadministration of atazanavir-ritonavir and zinc sulfate: impact on hyperbilirubinemia and pharmacokinetics. Antimicrob Agents Chemother. 2013 Aug PubMed
- Zittel S, Ufer F, Gerloff C, Münchau A, Rosenkranz M. Severe myelopathy after denture cream use--is copper deficiency or excess zinc the cause? Clin Neurol Neurosurg. 2014 Jun;121:17-8. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Guidelines for the Use of Antiretroviral Agents in HIV-1-Infected Adults and Adolescents: Drug Interactions between Integrase Inhibitors and Other Drugs. AIDSinfo. July 14, 2016. Available at: https://aidsinfo.nih.gov/guidelines/html/1/adult-and-adolescen
- Ding Y, Jia YY, Li F, et al. The effect of staggered administration of zinc sulfate on the pharmacokinetics of oral cephalexin. Br J Clin Pharmacol. 2012 Mar;73(3):422-7. PubMed
- Fallah R, Sabbaghzadegan S, Karbasi SA, Binesh F. Efficacy of zinc sulfate supplement on febrile seizure recurrence prevention in children with normal serum zinc level: A randomised clinical trial. Nutrition. 2015;31(11-12):1358-61. PubMed
- Lazzerini M, Wanzira H. Oral zinc for treating diarrhoea in children. Cochrane Database Syst Rev. 2016;12:CD005436. PubMed
- Mahmoud AM, Al-Alem U, Dabbous F, et al. Zinc intake and risk of prostate cancer: Case-control study and meta-analysis. PLoS One. 2016;11(11):e0165956. PubMed
- Nagraj SK, George RP, Shetty N, Levenson D, Ferraiolo DM, Shrestha A. Interventions for managing taste disturbances. Cochrane Database Syst Rev. 2017 Dec 20;12(12):CD010470. PubMed
- Yee BE, Richards P, Sui JY, Marsch AF. Serum zinc levels and efficacy of zinc treatment in acne vulgaris: A systematic review and meta-analysis. Dermatol Ther. 2020:e14252. PubMed
- Janyajirawong R, Vilaichone RK, Sethasine S. Efficacy of zinc supplement in minimal hepatic encephalopathy: A prospective, randomized controlled study (Zinc-MHE Trial). Asian Pac J Cancer Prev 2021;22(9):2879-2887. PubMed
- Nakano M, Nakamura Y, Miyazaki A, Takahashi J. Zinc pharmacotherapy for elderly osteoporotic patients with zinc deficiency in a clinical setting. Nutrients 2021;13(6):1814. PubMed
- Tolino E, Skroza N, Mambrin A, et al. An open-label study comparing oral zinc to lymecycline in the treatment of acne vulgaris. J Clin Aesthet Dermatol 2021;14(5):56-58.
- Hunter J, Arentz S, Goldenberg J, et al. Zinc for the prevention or treatment of acute viral respiratory tract infections in adults: a rapid systematic review and meta-analysis of randomised controlled trials. BMJ Open. 2021;11(11):e047474. PubMed
- Yamazaki K, Kageyama H, Fujiyama T, Ito T, Urano S, Honda T. A case of systemic contact dermatitis due to zinc supplements. Int J Dermatol 2022. PubMed
- Magham K, Han J, Eilbert W, Bunney EB. Severe copper deficiency anemia caused by zinc supplement use. Am J Emerg Med 2023;72:222. PubMed
- Sivakumar RR, Chinnaiah Govindareddy D, Sahoo J, Bobby Z, Chinnakali P. Effect of daily zinc supplementation for 12 weeks on serum thyroid auto-antibody levels in children and adolescents with autoimmune thyroiditis - a randomized controlled trial. J Pedi PubMed
- AlDhasee O, AlMalki H, AlKharashi N, AlJeraisy N, Al Deeb M. Acute zinc sulfate overdose: clinical presentation and management. BMJ Case Rep 2025;18(1):e263899. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Vitamin D 26 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Tatro DS, ed. Drug Interactions Facts. Facts and Comparisons Inc., St. Louis, MO. 1999.
- Koutkia P, Chen TC, Holick MF. Vitamin D intoxication associated with an over-the-counter supplement. N Engl J Med 2001;345:66-7. PubMed
- Bar-Or D, Yoel G. Calcium and calciferol antagonize effect of verapamil in atrial fibrillation. Br Med J 1981;282:1585-6.
- Demontis R, Leflon A, Fournier A, et al. 1 alpha(OH) vitamin D3 increases plasma aluminum in hemodialyzed patients taking AI(OH)3. Clin Nephrol 1986;26:146-9.
- Crowe M, Wollner L, Griffiths RA. Hypercalcemia following vitamin D and thiazide therapy in the elderly. Practitioner 1984;228:312-3.
- Parfitt AM. Thiazide-induced hypercalcemia in vitamin D-treated hypoparathyroidism. Ann Intern Med 1972;77:557-63. PubMed
- Thiazide diuretics and the risk of osteoporosis. Pharmacist's Letter/Prescriber's Letter 2003;19(11):191105.
- Moon J. The role of vitamin D in toxic metal absorption. J Am Coll Nutr 1994;13:559-64.
- Demontis R, Reissi D, Noel C, et al. Indirect clinical evidence that 1alphaOH vitamin D<SUB>3</SUB> increases the intestinal absorption of aluminum. Clin Nephrol 1989;31:123-7.
- Adler AJ, Berlyne GM. Duodenal aluminum absorption in the rat: effect of vitamin D. Am J Physiol 1985;249:G209-13. PubMed
- Schwartz JB. Effects of vitamin D supplementation in atorvastatin-treated patients: A new drug interaction with an unexpected consequence. Clin Pharmacol Ther 2009;85:198-203. PubMed
- Dietary reference intakes for calcium and vitamin D. Institute of Medicine, November 30, 2010. Available at: http://www.iom.edu/~/media/Files/Report%20Files/2010/Dietary-Reference-Intakes-for-Calcium-and-Vitamin-D/Vitamin%20D%20and%20Calcium%202010%20Repo
- Cox KA, Dunn MA. Aluminum toxicity alters the regulation of calbindin-D28k protein and mRNA expression in chick intestine. J Nutr 2001;131:2007-13. PubMed
- Escribano, J., Balaguer, A., Pagone, F., Feliu, A., and Roque, I. Figuls. Pharmacological interventions for preventing complications in idiopathic hypercalciuria. Cochrane.Database.Syst.Rev. 2009;(1):CD004754. PubMed
- Carlton, S., Clopton, D., and Cappuzzo, K. A. Vitamin D deficiency: appropriate replenishment therapies and the effects of vitamin D toxicity. Consult Pharm 2010;25(3):171-177. PubMed
- Wang, H., Xia, N., Yang, Y., and Peng, D. Q. Influence of vitamin D supplementation on plasma lipid profiles: a meta-analysis of randomized controlled trials. Lipids Health Dis. 2012;11:42. PubMed
- Turner AN, Carr Reese P, Fields KS, Anderson J, Ervin M, Davis JA, Fichorova RN, Roberts MW, Klebanoff MA, Jackson RD. A blinded, randomized controlled trial of high-dose vitamin D supplementation to reduce recurrence of bacterial vaginosis. Am J Obstet G PubMed
- Weiner M, Epstein FH. Signs and symptoms of electrolyte disorders. Yale J Biol Med. 1970;43(2):76-109.
- Lappe J, Watson P, Travers-Gustafson D, Recker R, Garland C, Gorham E, Baggerly K, McDonnell SL. Effect of Vitamin D and Calcium Supplementation on Cancer Incidence in Older Women: A Randomized Clinical Trial. JAMA. 2017 Mar 28;317(12):1234-1243. PubMed
- Roth DE, Leung M, Mesfin E, Qamar H, Watterworth J, Papp E. Vitamin D supplementation during pregnancy: state of the evidence from a systematic review of randomised trials. BMJ. 2017;359:j5237. PubMed
- Murai IH, Fernandes AL, Sales LP, et al. Effect of a single high dose of vitamin D3 on hospital length of stay in patients with moderate to severe COVID-19: A randomized clinical trial. JAMA. 2021.
- Wang Z, Schuetz EG, Xu Y, Thummel KE. Interplay between vitamin D and the drug metabolizing enzyme CYP3A4. J Steroid Biochem Mol Biol 2013;136:54-8. PubMed
- Doyle D, Browne U, Brickley A, Murphy D. Vitamin D-induced hypercalcaemia and acute kidney injury in sarcoidosis. BMJ Case Rep 2023;16(1):e250580. PubMed
- Williamson A, Martineau AR, Sheikh A, Jolliffe D, Griffiths CJ. Vitamin D for the management of asthma. Cochrane Database Syst Rev 2023;2(2):CD011511. PubMed
- Kinesya E, Santoso D, Gde Arya N, et al. Vitamin D as adjuvant therapy for diabetic foot ulcers: Systematic review and meta-analysis approach. Clin Nutr ESPEN 2023;54:137-143. PubMed
Vitamin E 64 references
- Kim JM, White RH. Effect of vitamin E on the anticoagulant response to warfarin. Am J Cardiol 1996;77:545-6. PubMed
- Corrigan JJ Jr. The effect of vitamin E on warfarin-induced vitamin K deficiency. Ann N Y Acad Sci 1982;393:361-8. PubMed
- Corrigan JJ Jr. Coagulation problems relating to vitamin E. Am J Pediatr Hematol Oncol 1979;1:169-73.
- Corrigan JJ Jr, Marcus FI. Coagulopathy associated with vitamin E ingestion. JAMA 1974;230:1300-1. DOI
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Chang T, Benet LZ, Hebert MF. The effect of water-soluble vitamin E on cyclosporine pharmacokinetics in healthy volunteers. Clin Pharmacol Ther 1996;59:297-303. PubMed
- Pan SH, Lopez RR Jr, Sher LS, et al. Enhanced oral cyclosporine absorption with water-soluble vitamin E early after liver transplantation. Pharmacother 1996;16:59-65. DOI
- Anon. Dietary supplementation with n-3 polyunsaturated fatty acids and vitamin E after myocardial infarction: results of the GISSI-Prevenzione trial. Gruppo Italiano per lo Studio della Soprawivenza nell'Infarto miocardico. Lancet 1999;354:447-55. DOI
- Chappell LC, Seed PT, Briley AL, et al. Effect of antioxidants on the occurrence of pre-eclampsia in women at increased risk: a randomised trial. Lancet 1999;354:810-6. DOI
- Yusuf S, Dagenais G, Pogue J, et al. Vitamin E supplementation and cardiovascular events in high-risk patients. The heart outcomes prevention evaluation study investigators. N Engl J Med 2000;342:154-60. PubMed
- Stephens NG, Parsons A, Schofield PM, et al. Randomised controlled trial of vitamin E in patients with coronary disease: Cambridge Heart Antioxidant Study. Lancet 1996;347:781-6.
- The Alpha-Tocopherol, Beta Carotene Cancer Prevention Study Group. The effect of vitamin E and beta carotene on the incidence of lung cancer and other cancers in male smokers. N Engl J Med 1994;330:1029-35. PubMed
- Takahashi O. Haemorrhagic toxicity of a large dose of alpha-, beta-, gamma- and delta-tocopherols, ubiquinone, beta-carotene, retinol acetate and L-ascorbic acid in the rat. Food Chem Toxicol 1995;33:121-8.
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Sano M, Ernesto C, Thomas RG, et al. A controlled trial of selegiline, alpha-tocopherol, or both as treatment for Alzheimer's disease. The Alzheimer's Disease Cooperative Study. N Engl J Med 1997;336:1216-22. PubMed
- Liede KE, Haukka JK, Saxen LM, Heinonen OP. Increased tendency towards gingival bleeding caused by joint effect of alpha-tocopherol supplementation and acetylsalicylic acid. Ann Med 1998;30:542-6.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Liu M, Wallmon A, Olsson-Mortlock C, et al. Mixed tocopherols inhibit platelet aggregation in humans: potential mechanisms. Am J Clin Nutr 2003;77:700-6. PubMed
- Sokol RJ, Johnson KE, Karrer FM, et al. Improvement of cyclosporin absorption in children after liver transplantation by means of water-soluble vitamin E. Lancet 1991;338:212-4.. PubMed
- Stein JH, Carlsson CM, Papcke-Benson K, et al. The effects of lipid-lowering and antioxidant vitamin therapies on flow-mediated vasodilation of the brachial artery in older adults with hypercholesterolemia. J Am Coll Cardiol 2001;38:1806-13.. PubMed
- Carlsson CM, Papcke-Benson K, Carnes M, et al. Health-related quality of life and long-term therapy with pravastatin and tocopherol (vitamin E) in older adults. Drugs Aging 2002;19:793-805. . PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Schrogie JJ. Coagulopathy and fat-soluble vitamins (letter). JAMA 1975;232:19. DOI
- Celestini A, Pulcinelli FM, Pignatelli P, et al. Vitamin E potentiates the antiplatelet activity of aspirin in collagen-stimulated platelets. Haematologica 2002;87:420-6.
- Stampfer MJ, Jakubowski JA, Faigel D, et al. Vitamin E supplementation effect on human platelet function, arachidonic acid metabolism, and plasma prostacyclin levels. Am J Clin Nutr 1988;47:700-6. PubMed
- Jandak J, Steiner M, Richardson PD. Alpha-tocopherol, an effective inhibitor of platelet adhesion. Blood 1989;73:141-9. DOI
- Freedman JE, Farhat JH, Loscalzo J, Keaney JF. Alpha-tocopherol inhibits aggregation of human platelets by a protein kinase C-dependent mechanism. Circulation 1996;94:2434-40. PubMed
- Steiner M. Vitamin E, a modifier of platelet function: rationale and use in cardiovascular and cerebrovascular disease. Nutr Rev 1999;57:306-9. PubMed
- Brodkin RH, Bleiberg J. Sensitivity to topically applied vitamin E. Arch Dermatol 1965;92:76-7. DOI
- Booth SL, Golly I, Sacheck JM, et al. Effect of vitamin E supplementation on vitamin K status in adults with normal coagulation status. Am J Clin Nutr 2004;80:143-8. PubMed
- Miller ER 3rd, Pastor-Barriuso R, Dalal D, et al. Meta-analysis: High-dosage vitamin E supplementation may increase all-cause mortality. Ann Intern Med 2005;142:60520-53. PubMed
- Lonn E, Bosch J, Yusuf S, et al. HOPE and HOPE-TOO Trial Investigators. Effects of long-term vitamin E supplementation on cardiovascular events and cancer: a randomized controlled trial. JAMA 2005;293:1338-47. PubMed
- Landes N, Pfluger P, Kluth D, et al. Vitamin E activates gene expression via the pregnane X receptor. Biochem Pharmacol 2003;65:269-73. . PubMed
- Brigelius-Flohe R. Vitamin E and drug metabolism. Biochem Biophys Res Commun 2003;305:737-40. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Schurks M, Glynn RJ, Rist PM, et al. Effects of vitamin E on stroke subtypes: meta-analysis of randomized controlled trials. BMJ 2010;341: c5702. doi: 10.1136/bmj.c5702.
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Gaziano JM, Glynn RJ, Christen WG, et al. Vitamins E and C in the prevention of prostate total cancer in men: the physicians' health study II randomised controlled trial. JAMA 2009;301:52-62.
- Hayden KM, Welsh-Bohmer KA, Wengreen HJ, et al; Cache County Investigators. Risk of mortality with vitamin E supplements: the Cache County study. Am L Med 2007;120:180-4. PubMed
- Smedts HP, de Vries JH, Rakhshandehroo M, et al. High maternal vitamin E intake by diet or supplements is associated with congenital heart defects in the offspring. BJOG 2009;116:416-23. PubMed
- Klein EA, Thompson IM Jr, Tangen CM, et al. Vitamin E and the risk of prostate cancer: the Selenium and Vitamin E Cancer Prevention Trial (SELECT). JAMA 2011;306:1549-56. PubMed
- Huang, H. Y., Caballero, B., Chang, S., Alberg, A. J., Semba, R. D., Schneyer, C. R., Wilson, R. F., Cheng, T. Y., Vassy, J., Prokopowicz, G., Barnes, G. J., and Bass, E. B. The efficacy and safety of multivitamin and mineral supplement use to prevent ca
- Sesso, H. D., Buring, J. E., Christen, W. G., Kurth, T., Belanger, C., MacFadyen, J., Bubes, V., Manson, J. E., Glynn, R. J., and Gaziano, J. M. Vitamins E and C in the prevention of cardiovascular disease in men: the Physicians' Health Study II randomiz
- Papaioannou, D., Cooper, K. L., Carroll, C., Hind, D., Squires, H., Tappenden, P., and Logan, R. F. Antioxidants in the chemoprevention of colorectal cancer and colorectal adenomas in the general population: a systematic review and meta-analysis. Colorec PubMed
- Cooper, K., Squires, H., Carroll, C., Papaioannou, D., Booth, A., Logan, R. F., Maguire, C., Hind, D., and Tappenden, P. Chemoprevention of colorectal cancer: systematic review and economic evaluation. Health Technol.Assess. 2010;14(32):1-206. PubMed
- Mathew, M. C., Ervin, A. M., Tao, J., and Davis, R. M. Antioxidant vitamin supplementation for preventing and slowing the progression of age-related cataract. Cochrane.Database.Syst.Rev. 2012;6:CD004567. PubMed
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Soares, K. V. and McGrath, J. J. Vitamin E for neuroleptic-induced tardive dyskinesia. Cochrane.Database.Syst.Rev. 2001;(4):CD000209. DOI
- Roed-Petersen, J. and Hjorth, N. Contact dermatitis from antioxidants. Br.J.Dermatol. 1976;94(3):233-241. PubMed
- Brion, L. P., Bell, E. F., Raghuveer, T. S., and Soghier, L. What is the appropriate intravenous dose of vitamin E for very-low-birth-weight infants? J.Perinatol. 2004;24(4):205-207. PubMed
- Manny, T., Pettus, J., Hemal, A., Marks, M., and Mirzazadeh, M. Penile sclerosing lipogranulomas and disfigurement from use of "1Super Extenze" among Laotian immigrants. J.Sex Med. 2011;8(12):3505-3510. PubMed
- Musso, G., Cassader, M., Rosina, F., and Gambino, R. Impact of current treatments on liver disease, glucose metabolism and cardiovascular risk in non-alcoholic fatty liver disease (NAFLD): a systematic review and meta-analysis of randomised trials. Diabe PubMed
- Bell, E. F. Upper limit of vitamin E in infant formulas. J.Nutr. 1989;119(12 Suppl):1829-1831. PubMed
- Manzano, D., Aguirre, A., Gardeazabal, J., Eizaguirre, X., and Diaz Perez, J. L. Allergic contact dermatitis from tocopheryl acetate (vitamin E) and retinol palmitate (vitamin A) in a moisturizing cream. Contact Dermatitis 1994;31(5):324.
- Barak, Y., Swartz, M., Shamir, E., Stein, D., and Weizman, A. Vitamin E (alpha-tocopherol) in the treatment of tardive dyskinesia: a statistical meta-analysis. Ann.Clin.Psychiatry 1998;10(3):101-105.
- Chae CU, Albert CM, Moorthy MV, et al. Vitamin E supplementation and the risk of heart failure in women. Circ Heart Fail. 2012;5(2):176-82. PubMed
- Rumbold A, Ota E, Hori H, Miyazaki C, Crowther CA. Vitamin E supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004069. PubMed
- Prescribing information: KOSELUGO (selumetinib) capsules. U.S. Food and Drug Administration. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2020/213756s000lbl.pdf.
- Warshaw EM, Ruggiero JL, DeKoven JG, et al. Patch testing with tocopherol and tocopherol acetate: the North American Contact Dermatitis Group experience, 2001 to 2016. Dermatitis. 2021;32(5):308-18. PubMed
- US Preventive Services Task Force, Mangione CM, Barry MJ, et al. Vitamin, Mineral, and Multivitamin Supplementation to Prevent Cardiovascular Disease and Cancer: US Preventive Services Task Force Recommendation Statement. JAMA 2022;327(23):2326-2333. PubMed
- Abrol R, Kaushik R, Goel D, Sama S, Kaushik RM, Kala M. Vitamin E-induced coagulopathy in a young patient: a case report. J Med Case Rep 2023;17(1):107. PubMed
- Abtahi-Naeini B, Rastegarnasab F, Saffaei A. Liquid vitamin E injection for cosmetic facial rejuvenation: A disaster report of lipogranuloma. J Cosmet Dermatol 2022;21(11):5549-5554. PubMed
Docosahexaenoic Acid (dha) 49 references
- Akedo I, Ishikawa H, Nakamura T, et al. Three cases with familial adenomatous polyposis diagnosed as having malignant lesions in the course of a long-term trial using docosahexanoic acid (DHA)-concentrated fish oil capsules (abstract). Jpn J Clin Oncol PubMed
- Prisco D, Paniccia R, Bandinelli B, et al. Effect of medium-term supplementation with a moderate dose of n-3 polyunsaturated fatty acids on blood pressure in mild hypertensive patients. Thromb Res 1998;1:105-12.
- Grimsgaard S, Bonaa KH, Hansen JB, Nordoy A. Highly purified eicosapentaenoic acid and docosahexaenoic acid in humans have similar triacylglycerol-lowering effects but divergent effects on serum fatty acids. Am J Clin Nutr 1997;66:649-59.
- Toft I, Bonaa KH, Ingebretsen OC, et al. Effects of n-3 polyunsaturated fatty acids on glucose homeostasis and blood pressure in essential hypertension. A randomized, controlled trial. Ann Intern Med 1995;123:911-8.
- Sacks FM, Hebert P, Appel LJ, et al. Short report: the effect of fish oil on blood pressure and high-density lipoprotein-cholesterol levels in phase I of the trials of hypertension prevention. J Hypertens 1994;12:209-13.
- Vandongen R, Mori TA, Burke V, et al. Effects on blood pressure of omega 3 fats in subjects at increased risk of cardiovascular disease. Hypertension 1993;22:371-9. PubMed
- FDA. Center for Food Safety and Applied Nutrition. Letter regarding dietary supplement health claim for omega-3 fatty acids and coronary heart disease. Available at: http://www.fda.gov/ohrms/dockets/dockets/95s0316/95s-0316-Rpt0272-38-Appendix-D-Reference
- Pedersen HS, Mulvad G, Seidelin KN, et al. N-3 fatty acids as a risk factor for haemorrhagic stroke. Lancet 1999;353:812-3. PubMed
- Ito Y, Suzuki K, Imai H, et al. Effects of polyunsaturated fatty acids on atrophic gastritis in a Japanese population. Cancer Lett 2001;163:171-8. PubMed
- Kris-Ehterton PM, Harris WS, Appel LJ, et al. Fish consumption, fish oil, omega-3 fatty acids, and cardiovascular disease. Circulation 2002;106:2747-57. PubMed
- Woodman RJ, Mori TA, Burke V, et al. Effects of purified eicosapentaenoic and docosahexaenoic acids on glycemic control, blood pressure, and serum lipids in type 2 diabetic patients with treated hypertension. Am J Clin Nutr 2002;76:1007-15.. PubMed
- Marangell LB, Martinez JM, Zboyan HA, et al. A double-blind, placebo-controlled study of the omega-3 fatty acid docosahexaenoic acid in the treatment of major depression. Am J Psychiatry 2003;160:996-8.. PubMed
- Leng GC, Smith FB, Fowkes FG, et al. Relationship between plasma essential fatty acids and smoking, serum lipids, blood pressure and haemostatic and rheological factors. Prostaglandins Leukot Essent Fatty Acids 1994;51:101-8. PubMed
- Nelson GJ, Schmidt PS, Bartolini GL, et al. The effect of dietary docosahexaenoic acid on platelet function, platelet fatty acid composition, and blood coagulation in humans. Lipids 1997;32:1129-36. PubMed
- Wheaton DH, Hoffman DR, Locke KG, et al. Biological safety assessment of docosahexaenoic acid supplementation in a randomized clinical trial for X-linked retinitis pigmentosa. Arch Ophthalmol 2003;121:1269-78. PubMed
- Malcolm CA, McCulloch DL, Montgomery C, et al. Maternal docosahexaenoic acid supplementation during pregnancy and visual evoked potential development in term infants: a double blind, prospective, randomised trial. Arch Dis Child Fetal Neonatal Ed 2003;88: DOI
- Sanjurjo P, Ruiz-Sanz JI, Jimeno P, et al. Supplementation with docosahexaenoic acid in the last trimester of pregnancy: maternal-fetal biochemical findings. J Perinat Med 2004;32:132-6.
- Montgomery C, Speake BK, Cameron A, et al. Maternal docosahexaenoic acid supplementation and fetal accretion. Br J Nutr 2003;90:135-45. DOI
- Lauritzen L, Hoppe C, Straarup EM, Michaelsen KF. Maternal fish oil supplementation in lactation and growth during the first 2.5 years of life. Pediatr Res 2005;58:235-42. PubMed
- Hawkes JS, Bryan DL, Makrides M, et al. A randomized trial of supplementation with docosahexaenoic acid-rich tuna oil and its effects on the human milk cytokines interleukin 1 beta, interleukin 6, and tumor necrosis factor alpha. Am J Clin Nutr 2002;75:75
- Uauy R, Hoffman DR, Mena P, et al. Term infant studies of DHA and ARA supplementation on neurodevelopment: Results of randomized controlled trials. J Pediatr 2003;143:S17-25. PubMed
- Decsi, T., Campoy, C., and Koletzko, B. Effect of N-3 polyunsaturated fatty acid supplementation in pregnancy: the Nuheal trial. Adv.Exp Med Biol 2005;569:109-113. PubMed
- Mori, T. A., Bao, D. Q., Burke, V., Puddey, I. B., and Beilin, L. J. Docosahexaenoic acid but not eicosapentaenoic acid lowers ambulatory blood pressure and heart rate in humans. Hypertension 1999;34(2):253-260. PubMed
- Otto, S. J., van Houwelingen, A. C., and Hornstra, G. The effect of supplementation with docosahexaenoic and arachidonic acid derived from single cell oils on plasma and erythrocyte fatty acids of pregnant women in the second trimester. Prostaglandins Le PubMed
- Helland, I. B., Saugstad, O. D., Smith, L., Saarem, K., Solvoll, K., Ganes, T., and Drevon, C. A. Similar effects on infants of n-3 and n-6 fatty acids supplementation to pregnant and lactating women. Pediatrics 2001;108(5):E82. PubMed
- Nestel, P., Shige, H., Pomeroy, S., Cehun, M., Abbey, M., and Raederstorff, D. The n-3 fatty acids eicosapentaenoic acid and docosahexaenoic acid increase systemic arterial compliance in humans. Am.J.Clin.Nutr. 2002;76(2):326-330. PubMed
- Woodman, R. J., Mori, T. A., Burke, V., Puddey, I. B., Barden, A., Watts, G. F., and Beilin, L. J. Effects of purified eicosapentaenoic acid and docosahexaenoic acid on platelet, fibrinolytic and vascular function in hypertensive type 2 diabetic patients PubMed
- Jensen, C. L., Voigt, R. G., Prager, T. C., Zou, Y. L., Fraley, J. K., Rozelle, J. C., Turcich, M. R., Llorente, A. M., Anderson, R. E., and Heird, W. C. Effects of maternal docosahexaenoic acid intake on visual function and neurodevelopment in breastfed
- Theobald, H. E., Goodall, A. H., Sattar, N., Talbot, D. C., Chowienczyk, P. J., and Sanders, T. A. Low-dose docosahexaenoic acid lowers diastolic blood pressure in middle-aged men and women. J Nutr 2007;137(4):973-978.
- Mischoulon D, Best-Popescu C, Laposata M, et al. A double-blind dose-finding pilot study of docosahexaenoic acid (DHA) for major depressive disorder. Eur Neuropsychopharmacol. 2008;18(9):639-645. PubMed
- Birch EE, Carlson SE, Hoffman DR, et al. The DIAMOND (DHA Intake And Measurement Of Neural Development) Study: a double-masked, randomized controlled clinical trial of the maturation of infant visual acuity as a function of the dietary level of docosahexa
- Carlson SE, Colombo J, Gajewski BJ, Gustafson KM, Mundy D, Yeast J, Georgieff MK, Markley LA, Kerling EH, Shaddy DJ. DHA supplementation and pregnancy outcomes. Am J Clin Nutr. 2013 Apr;97(4):808-15. PubMed
- Escamilla-Nuñez MC, Barraza-Villarreal A, Hernández-Cadena L, Navarro-Olivos E, Sly PD, Romieu I. Omega-3 fatty acid supplementation during pregnancy and respiratory symptoms in children. Chest. 2014 Aug;146(2):373-82. PubMed
- Fu YQ, Zheng JS, Yang B, Li D. Effect of individual omega-3 fatty acids on the risk of prostate cancer: a systematic review and dose-response meta-analysis of prospective cohort studies. J Epidemiol. 2015;25(4):261-74. PubMed
- Imhoff-Kunsch B, Stein AD, Villalpando S, Martorell R, Ramakrishnan U. Docosahexaenoic acid supplementation from mid-pregnancy to parturition influenced breast milk fatty acid concentrations at 1 month postpartum in Mexican women. J Nutr. 2011 Feb;141(2): PubMed
- Judge MP, Cong X, Harel O, Courville AB, Lammi-Keefe CJ. Maternal consumption of a DHA-containing functional food benefits infant sleep patterning: an early neurodevelopmental measure. Early Hum Dev. 2012 Jul;88(7):531-7. PubMed
- Mulder KA, King DJ, Innis SM. Omega-3 fatty acid deficiency in infants before birth identified using a randomized trial of maternal DHA supplementation in pregnancy. PLoS One. 2014 Jan 10;9(1):e83764. PubMed
- Richardson AJ, Burton JR, Sewell RP, Spreckelsen TF, Montgomery P. Docosahexaenoic acid for reading, cognition and behavior in children aged 7-9 years: a randomized, controlled trial (the DOLAB Study). PLoS One. 2012;7(9):e43909. PubMed
- Drugs in Pregnancy and Lactation 2012;25(4);3-4
- FDA announces qualified health claims for omega-3 fatty acids. Available at: https://www.fda.gov/Food/LabelingNutrition/ucm072756.htm. Accessed April 15 2019.
- Breastfeeding and the use of human milk. Section on Breastfeeding. Pediatrics. 2012;129(3):e827-41. PubMed
- Zhang Z, Fulgoni VL, Kris-Etherton PM, Mitmesser SH. Dietary Intakes of EPA and DHA Omega-3 Fatty Acids among US Childbearing-Age and Pregnant Women: An Analysis of NHANES 2001-2014. Nutrients. 2018;10(4). PubMed
- Montgomery P, Spreckelsen TF, Burton A, Burton JR, Richardson AJ. Docosahexaenoic acid for reading, working memory and behavior in UK children aged 7-9: A randomized controlled trial for replication (the DOLAB II study). PLoS One. 2018;13(2):e0192909. PubMed
- Marc I, Piedboeuf B, Lacaze-Masmonteil T, et al. Effect of maternal docosahexaenoic acid supplementation on bronchopulmonary dysplasia-free survival in breastfed preterm infants: A randomized clinical trial. JAMA. 2020;324(2):157-167. PubMed
- Fougère H, Bilodeau JF, Lavoie PM, et al. Docosahexaenoic acid-rich algae oil supplementation on breast milk fatty acid profile of mothers who delivered prematurely: a randomized clinical trial. Sci Rep 2021;11(1):21492. PubMed
- Garmendia ML, Casanello P, Flores M, Kusanovic JP, Uauy R. The effects of a combined intervention (docosahexaenoic acid supplementation and home-based dietary counseling) on metabolic control in obese and overweight pregnant women: the MIGHT study. Am J O PubMed
- Christifano DN, Gustafson KM, Carlson SE, et al. Maternal docosahexaenoic acid exposure needed to achieve maternal-newborn EQ. Nutrients 2022;14(16):3300. PubMed
- Vizzari G, Morniroli D, Alessandretti F, et al. Comparative analysis of docosahexaenoic acid (DHA) content in mother's milk of term and preterm mothers. Nutrients 2022;14(21):4595. PubMed
- Yang Y, Li G, Li F, et al. Impact of DHA from algal oil on the breast milk DHA levels of lactating women: A randomized controlled trial in China. Nutrients 2022;14(16):3410. PubMed
See these in context on the Docosahexaenoic Acid (dha) monograph →
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC