
Madhunash Vati Tablets Ingredients & Drug Interactions
What is this page for?
First and foremost: checking Madhunash Vati Tablets against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
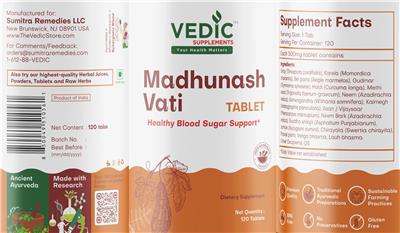
Madhunash Vati Tablets is a dietary supplement by Vedic Supplements with 17 active ingredients. Its ingredients are commonly taken for diarrhea and dysentery, indigestion and other digestive complaints, constipation.Based on those ingredients, 1,596 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Ashwagandha, Curcuma longa, Neem. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Madhunash Vati Tablets by Vedic Supplements
Ask about any prescription or over-the-counter medication and we check it for interactions with Madhunash Vati Tablets by Vedic Supplements — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Madhunash Vati Tablets by Vedic Supplements
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Low disclosure
Madhunash Vati Tablets contains 17 ingredients. The active ingredients include bael (Aegle marmelos), bitter melon (Momordica charantia), gymnema (Gymnema sylvestre), ashwagandha, Pterocarpus marsupium, neem, Tinospora cordifolia, andrographis, turmeric (Curcuma longa), fenugreek (Trigonella foenum-graecum), shilajit, jambolan (Syzygium cumini), chirata (Swertia chirayita), and praval pishti (a calcium preparation).
Three ingredients — Pterocarpus marsupium, Vanga bhasma, and Lauh bhasma — we were unable to check for interaction data. There are no inactive fillers listed.
Does it work?
Moderate evidence
The evidence for Madhunash Vati is mixed. Tinospora cordifolia and fenugreek are rated Possibly Effective for diabetes, and ashwagandha is Possibly Effective for insomnia, anxiety, stress, and generalized anxiety disorder.
Turmeric shows possible effectiveness for depression, high cholesterol, allergic rhinitis, and digestive upset. Andrographis is rated Possibly Effective for ulcerative colitis, sore throat, and osteoarthritis, while neem is Possibly Effective for gum disease and lice.
For most other uses this product claims — asthma, constipation, liver disease, and others — the evidence we hold rates them as Insufficient Reliable Evidence To Rate. This product's name suggests it's for blood sugar management, but we don't have established effectiveness data specifically for that purpose.
How safe is it?
Well-documented data
Several ingredients in this product carry pregnancy warnings. Bael, bitter melon, gymnema, ashwagandha, neem, andrographis, Tinospora cordifolia, fenugreek, shilajit, jambolan, and chirata should all be avoided during pregnancy because the safety data advises against it or is insufficient.
For breastfeeding, similar caution applies — most of these ingredients lack adequate safety data while nursing, though fenugreek is traditionally used to boost milk supply (discuss with your provider first). The most common side effects are gastrointestinal: bitter melon and bael may cause stomach upset and constipation, while fenugreek and other ingredients can cause abdominal discomfort, diarrhea, nausea, and flatulence.
Rare but serious concerns include liver injury (reported with ashwagandha, turmeric, and Tinospora cordifolia), kidney injury (bitter melon in one case), hemolytic anemia (neem in people with certain genetic conditions), and severe allergic reactions (andrographis and fenugreek). Shilajit carries contamination risk — use only purified, tested brands.
Meds to double-check
Major interaction found
Check your medications against these ingredient interactions before taking Madhunash Vati: HIV integrase inhibitors (dolutegravir, elvitegravir — calcium can significantly reduce their levels), antidiabetes drugs (multiple ingredients lower blood sugar), antihypertensive drugs (ashwagandha and andrographis may lower blood pressure further), blood thinners and antiplatelet drugs (andrographis, fenugreek, neem), hepatotoxic medications (ashwagandha, turmeric, Tinospora cordifolia), cytochrome P450 substrates like antidepressants and statins (bael, gymnema, neem, Tinospora cordifolia), thyroid medication (calcium and ashwagandha), and immunosuppressants (ashwagandha, neem, Tinospora cordifolia, andrographis).
The bottom line
Scorecard at a glanceFormula with limited ingredient disclosure with some supporting evidence for its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
This is a traditional Ayurvedic formula with multiple ingredients that lower blood sugar and affect how your body processes medications. If you have diabetes, take blood thinners, or are on any regular medications — especially HIV drugs, thyroid medication, or blood pressure drugs — talk to your pharmacist before starting.
Avoid this product if you're pregnant or breastfeeding. It's safest for people with mild digestive complaints or metabolic concerns who take few or no medications, but even then, quality control matters: source from a reputable brand.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 14 of 17 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Aug 22, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Madhunash Vati Tablets, straight from the product label.
| Brand | Vedic Supplements |
|---|---|
| Barcode (UPC) | 850049510561 |
| Net contents | 120 Tablet(s) |
| Market status | On market |
| Date entered into DSLD | Aug 22, 2025 |
| DSLD ID | 336178 |
| Product type | Other Combinations |
| Supplement form | Tablet Or Pill |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Vegetarian, Adult (18 - 50 Years), Gluten Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for Madhunash Vati Tablets by Vedic Supplements, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Ingredients | 0 NP | -- |
| Aegle marmelos | 0 NP | -- |
| Momordica charantia | 0 NP | -- |
| Gymnema sylvestre | 0 NP | -- |
| Ashwagandha | 0 NP | -- |
| Pterocarpus marsupium | 0 NP | -- |
| Neem | 0 NP | -- |
| Tinospora cordifolia | 0 NP | -- |
| Neem | 0 NP | -- |
| Andrographis paniculata | 0 NP | -- |
| Curcuma longa | 0 NP | -- |
| Trigonella foenum-graecum | 0 NP | -- |
| Shilajit | 0 NP | -- |
| Syzygium cumini | 0 NP | -- |
| Swertia chirayita | 0 NP | -- |
| Praval pishti | 0 NP | -- |
| Vanga bhasma | 0 NP | -- |
| Lauh bhasma | 0 NP | -- |
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formula
Ayurveda + Modern Research = Synergistic Blend
Ancient Ayurveda
100% Ayurvedic product
General Statements
Also try our highest-quality herbal juices, powders, tablets and raw herbs
Made with research Scan QR code and explore our product range The Vedic Store
Formulation
100% Veg
Product of India
Healthy blood sugar support
Premium quality Traditional ayurvedic preparations Sustainable farming practices
BPA free No preservatives Gluten free
Brand IP Statement(s)
Vedic Supplements Your Health Matters
FDA Statement of Identity
Dietary Supplement
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Madhunash Vati Tablets by Vedic Supplements label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Madhunash Vati Tablets by Vedic Supplements
These are the 17 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Tab(s) Dosage formTablet Or Pill Servings per container120 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Ingredients
- › Aegle marmelos
- › Momordica charantia
- › Gymnema sylvestre
- › Ashwagandha
- › Pterocarpus marsupium
- › Neem
- › Tinospora cordifolia
- › Neem
- › Andrographis paniculata
- › Curcuma longa
- › Trigonella foenum-graecum
- › Shilajit
- › Syzygium cumini
- › Swertia chirayita
- › Praval pishti
- › Vanga bhasma
- › Lauh bhasma
Madhunash Vati Tablets by Vedic Supplements Drug Interactions
HelloPharmacist Interaction Report
Madhunash Vati Tablets by Vedic Supplements contains 17 ingredients, several of which interact with medications.
The most serious interaction we've documented is with calcium (praval pishti), which can significantly reduce blood levels of the HIV integrase inhibitor dolutegravir — a Major-severity interaction that requires timing your doses at least 2 hours apart before or 6 hours after taking calcium.
Read the full breakdown — every affected drug type, severity by severity
Beyond that, multiple ingredients pose Moderate-severity risks with common drug classes. Bael, bitter melon, gymnema, ashwagandha, neem, Tinospora cordifolia, and turmeric all interact with antidiabetes drugs and can increase the risk of low blood sugar (hypoglycemia).
Ashwagandha and andrographis may lower blood pressure and could compound the effects of antihypertensive medications. Ashwagandha, turmeric, and Tinospora cordifolia have also been linked to liver injury in rare cases, which is a concern if you're taking other hepatotoxic drugs such as methotrexate.
Several ingredients affect how your liver metabolizes drugs through the cytochrome P450 system — bael, gymnema, neem, and Tinospora cordifolia can all influence CYP enzymes and alter levels of medications including certain antidepressants, blood thinners, and statins. Bitter melon and neem also inhibit a cellular pump called P-glycoprotein, which can increase levels of some cancer drugs and cardiac medications.
Additionally, andrographis and fenugreek have antiplatelet effects and may interact with blood thinners like warfarin.
We could not check Pterocarpus marsupium, Vanga bhasma, or Lauh bhasma — no interaction data are on file for those ingredients. Altogether, these interactions span 1,573 individual medications.
Before you start this product, run your exact medications through the checker on this page.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Madhunash Vati Tablets?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Madhunash Vati Tablets interact with 1,596 drugs. Click any drug to see the details.
13 of the 17 ingredients in Madhunash Vati Tablets interact with drugs. Each result below shows which ingredient is responsible. Ashwagandha Curcuma longa Neem Gymnema sylvestre Aegle marmelos Tinospora cordifolia Andrographis paniculata Trigonella foenum-graecum Momordica charantia Syzygium cumini Praval pishti Shilajit Swertia chirayita
CeftriaxoneRocephin
How Ceftriaxone interacts with Madhunash Vati Tablets — through 1 ingredient. Tap an ingredient for the detail:
Praval PishtiCeftriaxone (rocephin) Major
Interaction Summary
Co-administration of intravenous calcium and ceftriaxone can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys.
Read the full Praval Pishti + Ceftriaxone interactionCobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide FumarateGenvoya
How Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interacts with Madhunash Vati Tablets — through 7 ingredients. Tap an ingredient for the detail:
Praval PishtiElvitegravir (vitekta), Bictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Major
Interaction Summary
Calcium seems to reduce levels of elvitegravir.
Read the full Praval Pishti + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionCurcuma LongaHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Curcuma Longa + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionNeemCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Neem + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionMomordica CharantiaP-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, bitter melon might increase levels of P-glycoprotein substrates.
Read the full Momordica Charantia + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionAshwagandhaHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionGymnema SylvestreCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionAegle MarmelosCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Bael and its constituents marmelosin and marmesinin inhibited cytochrome P450 3A4 (CYP3A4) activity in vitro.
Read the full Aegle Marmelos + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionDolutegravirTivicay
How Dolutegravir interacts with Madhunash Vati Tablets — through 4 ingredients. Tap an ingredient for the detail:
Praval PishtiDolutegravir (tivicay) Major
Interaction Summary
Calcium seems to reduce levels of dolutegravir.
Read the full Praval Pishti + Dolutegravir interactionMomordica CharantiaP-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, bitter melon might increase levels of P-glycoprotein substrates.
Read the full Momordica Charantia + Dolutegravir interactionNeemP-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of P-glycoprotein substrates.
Read the full Neem + Dolutegravir interactionCurcuma LongaP-glycoprotein Substrates Minor
Interaction Summary
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
Read the full Curcuma Longa + Dolutegravir interactionDolutegravir, Emtricitabine, Tenofovir AlafenamideDolutegravir, Emtricitabine, Tenofovir Alafenamide
How Dolutegravir, Emtricitabine, Tenofovir Alafenamide interacts with Madhunash Vati Tablets — through 5 ingredients. Tap an ingredient for the detail:
Praval PishtiDolutegravir (tivicay), Bictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Major
Interaction Summary
Calcium seems to reduce levels of dolutegravir.
Read the full Praval Pishti + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionNeemP-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of P-glycoprotein substrates.
Read the full Neem + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionCurcuma LongaHepatotoxic Drugs, P-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Curcuma Longa + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionAshwagandhaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionMomordica CharantiaP-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, bitter melon might increase levels of P-glycoprotein substrates.
Read the full Momordica Charantia + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionDolutegravir, RilpivirineJuluca
How Dolutegravir, Rilpivirine interacts with Madhunash Vati Tablets — through 7 ingredients. Tap an ingredient for the detail:
Praval PishtiDolutegravir (tivicay) Major
Interaction Summary
Calcium seems to reduce levels of dolutegravir.
Read the full Praval Pishti + Dolutegravir, Rilpivirine interactionCurcuma LongaP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
Read the full Curcuma Longa + Dolutegravir, Rilpivirine interactionNeemCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Neem + Dolutegravir, Rilpivirine interactionMomordica CharantiaP-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, bitter melon might increase levels of P-glycoprotein substrates.
Read the full Momordica Charantia + Dolutegravir, Rilpivirine interactionAshwagandhaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha + Dolutegravir, Rilpivirine interactionAegle MarmelosCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Bael and its constituents marmelosin and marmesinin inhibited cytochrome P450 3A4 (CYP3A4) activity in vitro.
Read the full Aegle Marmelos + Dolutegravir, Rilpivirine interactionGymnema SylvestreCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre + Dolutegravir, Rilpivirine interactionElvitegravirVitekta
How Elvitegravir interacts with Madhunash Vati Tablets — through 6 ingredients. Tap an ingredient for the detail:
Praval PishtiElvitegravir (vitekta) Major
Interaction Summary
Calcium seems to reduce levels of elvitegravir.
Read the full Praval Pishti + Elvitegravir interactionNeemCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Neem + Elvitegravir interactionCurcuma LongaCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Curcuma Longa + Elvitegravir interactionAshwagandhaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha + Elvitegravir interactionAegle MarmelosCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Bael and its constituents marmelosin and marmesinin inhibited cytochrome P450 3A4 (CYP3A4) activity in vitro.
Read the full Aegle Marmelos + Elvitegravir interactionGymnema SylvestreCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre + Elvitegravir interactionElvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil FumarateStribild
How Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interacts with Madhunash Vati Tablets — through 6 ingredients. Tap an ingredient for the detail:
Praval PishtiElvitegravir (vitekta), Bictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Major
Interaction Summary
Calcium seems to reduce levels of elvitegravir.
Read the full Praval Pishti + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionCurcuma LongaCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Curcuma Longa + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionAshwagandhaCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionNeemCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Neem + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionGymnema SylvestreCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionAegle MarmelosCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Bael and its constituents marmelosin and marmesinin inhibited cytochrome P450 3A4 (CYP3A4) activity in vitro.
Read the full Aegle Marmelos + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with Madhunash Vati Tablets — through 5 ingredients. Tap an ingredient for the detail:
Tinospora CordifoliaImmunosuppressants Moderate
Interaction Summary
Theoretically, Tinospora cordifolia might reduce the effectiveness of immunosuppressants.
Read the full Tinospora Cordifolia + 6-mercaptopurine interactionAndrographis PaniculataImmunosuppressants Moderate
Interaction Summary
Theoretically, andrographis might interfere with the effects of immunosuppressive drugs.
Read the full Andrographis Paniculata + 6-mercaptopurine interactionCurcuma LongaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Curcuma Longa + 6-mercaptopurine interactionNeemImmunosuppressants Moderate
Interaction Summary
Theoretically, neem might decrease the effectiveness of immunosuppressants.
Read the full Neem + 6-mercaptopurine interactionAshwagandhaHepatotoxic Drugs, Immunosuppressants Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with Madhunash Vati Tablets — through 5 ingredients. Tap an ingredient for the detail:
NeemCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Neem + Ado-trastuzumab Emtansine interactionCurcuma LongaCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Curcuma Longa + Ado-trastuzumab Emtansine interactionGymnema SylvestreCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre + Ado-trastuzumab Emtansine interactionAegle MarmelosCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Bael and its constituents marmelosin and marmesinin inhibited cytochrome P450 3A4 (CYP3A4) activity in vitro.
Read the full Aegle Marmelos + Ado-trastuzumab Emtansine interactionAshwagandhaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with Madhunash Vati Tablets — through 2 ingredients. Tap an ingredient for the detail:
AshwagandhaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Abacavir Sulfate, Dolutegravir, Lamivudine interactionCurcuma LongaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Curcuma Longa + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with Madhunash Vati Tablets — through 2 ingredients. Tap an ingredient for the detail:
Curcuma LongaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Curcuma Longa + Abacavir, Lamivudine interactionAshwagandhaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Abacavir, Lamivudine interactionAbciximabReoPro
How Abciximab interacts with Madhunash Vati Tablets — through 3 ingredients. Tap an ingredient for the detail:
Andrographis PaniculataAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, andrographis might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Andrographis Paniculata + Abciximab interactionTrigonella Foenum-graecumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, fenugreek might have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Trigonella Foenum-graecum + Abciximab interactionCurcuma LongaAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Curcuma Longa + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with Madhunash Vati Tablets — through 5 ingredients. Tap an ingredient for the detail:
Curcuma LongaCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Curcuma Longa + Abemaciclib interactionNeemCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Neem + Abemaciclib interactionAegle MarmelosCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Bael and its constituents marmelosin and marmesinin inhibited cytochrome P450 3A4 (CYP3A4) activity in vitro.
Read the full Aegle Marmelos + Abemaciclib interactionGymnema SylvestreCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre + Abemaciclib interactionAshwagandhaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha + Abemaciclib interactionAbiraterone
How Abiraterone interacts with Madhunash Vati Tablets — through 5 ingredients. Tap an ingredient for the detail:
NeemCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Neem + Abiraterone interactionCurcuma LongaHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Curcuma Longa + Abiraterone interactionAshwagandhaHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Abiraterone interactionAegle MarmelosCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Bael and its constituents marmelosin and marmesinin inhibited cytochrome P450 3A4 (CYP3A4) activity in vitro.
Read the full Aegle Marmelos + Abiraterone interactionGymnema SylvestreCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with Madhunash Vati Tablets — through 5 ingredients. Tap an ingredient for the detail:
AshwagandhaHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Abiraterone Acetate interactionCurcuma LongaHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Curcuma Longa + Abiraterone Acetate interactionNeemCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Neem + Abiraterone Acetate interactionGymnema SylvestreCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre + Abiraterone Acetate interactionAegle MarmelosCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Bael and its constituents marmelosin and marmesinin inhibited cytochrome P450 3A4 (CYP3A4) activity in vitro.
Read the full Aegle Marmelos + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with Madhunash Vati Tablets — through 8 ingredients. Tap an ingredient for the detail:
Curcuma LongaAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Curcuma Longa + Abrocitinib interactionTrigonella Foenum-graecumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, fenugreek might have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Trigonella Foenum-graecum + Abrocitinib interactionNeemImmunosuppressants, Cytochrome P450 2c9 (cyp2c9) Substrates Moderate
Interaction Summary
Theoretically, neem might decrease the effectiveness of immunosuppressants.
Read the full Neem + Abrocitinib interactionGymnema SylvestreCytochrome P450 2c9 (cyp2c9) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase or decrease levels of drugs metabolized by CYP2C9.
Read the full Gymnema Sylvestre + Abrocitinib interactionAshwagandhaImmunosuppressants Moderate
Interaction Summary
Theoretically, taking ashwagandha might decrease the effects of immunosuppressants.
Read the full Ashwagandha + Abrocitinib interactionTinospora CordifoliaCytochrome P450 2c9 (cyp2c9) Substrates, Immunosuppressants +1 Moderate
Interaction Summary
Theoretically, Tinospora cordifolia might increase levels of drugs metabolized by CYP2C9.
Read the full Tinospora Cordifolia + Abrocitinib interactionAndrographis PaniculataAnticoagulant/antiplatelet Drugs, Immunosuppressants Moderate
Interaction Summary
Theoretically, andrographis might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Andrographis Paniculata + Abrocitinib interactionSyzygium CuminiCytochrome P450 2c9 (cyp2c9) Substrates Moderate
Interaction Summary
There is some in vitro evidence that jambolan can inhibit CYP2C9.
Read the full Syzygium Cumini + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with Madhunash Vati Tablets — through 6 ingredients. Tap an ingredient for the detail:
NeemP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of P-glycoprotein substrates.
Read the full Neem + Acalabrutinib interactionMomordica CharantiaP-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, bitter melon might increase levels of P-glycoprotein substrates.
Read the full Momordica Charantia + Acalabrutinib interactionCurcuma LongaCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Curcuma Longa + Acalabrutinib interactionAegle MarmelosCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Bael and its constituents marmelosin and marmesinin inhibited cytochrome P450 3A4 (CYP3A4) activity in vitro.
Read the full Aegle Marmelos + Acalabrutinib interactionGymnema SylvestreCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre + Acalabrutinib interactionAshwagandhaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Madhunash Vati Tablets — through 11 ingredients. Tap an ingredient for the detail:
ShilajitAntidiabetes Drugs Moderate
Interaction Summary
Taking shilajit with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Shilajit + Acarbose interactionTinospora CordifoliaAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, Tinospora cordifolia might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Read the full Tinospora Cordifolia + Acarbose interactionTrigonella Foenum-graecumAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, fenugreek seed might have additive hypoglycemic effects when used with antidiabetes drugs.
Read the full Trigonella Foenum-graecum + Acarbose interactionCurcuma LongaAntidiabetes Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking turmeric with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Curcuma Longa + Acarbose interactionSyzygium CuminiAntidiabetes Drugs Moderate
Interaction Summary
Animal research shows that jambolan seed and bark extracts can lower blood glucose levels.
Read the full Syzygium Cumini + Acarbose interactionAegle MarmelosAntidiabetes Drugs Moderate
Interaction Summary
Evidence from animal research suggests that extracts of bael seed and leaf can reduce blood glucose levels.
Read the full Aegle Marmelos + Acarbose interactionMomordica CharantiaAntidiabetes Drugs Moderate
Interaction Summary
Taking bitter melon with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Momordica Charantia + Acarbose interactionGymnema SylvestreAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking gymnema with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Gymnema Sylvestre + Acarbose interactionNeemAntidiabetes Drugs Moderate
Interaction Summary
Neem might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Read the full Neem + Acarbose interactionSwertia ChirayitaAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking chirata concomitantly with antidiabetes drugs may increase the risk of hypoglycemia.
Read the full Swertia Chirayita + Acarbose interactionAshwagandhaAntidiabetes Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Ashwagandha + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Madhunash Vati Tablets — through 4 ingredients. Tap an ingredient for the detail:
AshwagandhaHepatotoxic Drugs, Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Acebutolol interactionAndrographis PaniculataAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, andrographis might increase the risk of hypotension when used with antihypertensive drugs.
Read the full Andrographis Paniculata + Acebutolol interactionCurcuma LongaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Curcuma Longa + Acebutolol interactionTrigonella Foenum-graecumAntihypertensive Drugs Minor
Interaction Summary
Fenugreek may also have an additive effect on blood pressure-lowering medications.
Read the full Trigonella Foenum-graecum + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Madhunash Vati Tablets — through 3 ingredients. Tap an ingredient for the detail:
Andrographis PaniculataAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, andrographis might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Andrographis Paniculata + Acenocoumarol interactionCurcuma LongaAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Curcuma Longa + Acenocoumarol interactionTrigonella Foenum-graecumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, fenugreek might have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Trigonella Foenum-graecum + Acenocoumarol interactionAcepromazineAtravet
How Acepromazine interacts with Madhunash Vati Tablets — through 1 ingredient. Tap an ingredient for the detail:
AshwagandhaCns Depressants Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Ashwagandha + Acepromazine interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with Madhunash Vati Tablets — through 6 ingredients. Tap an ingredient for the detail:
Gymnema SylvestreCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP1A2.
Read the full Gymnema Sylvestre + Acetaminophen interactionCurcuma LongaHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Curcuma Longa + Acetaminophen interactionNeemCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP1A2 substrates.
Read the full Neem + Acetaminophen interactionAshwagandhaHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Acetaminophen interactionTinospora CordifoliaCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Tinospora cordifolia might increase levels of drugs metabolized by CYP1A2.
Read the full Tinospora Cordifolia + Acetaminophen interactionAegle MarmelosCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Bael extract and its constituent marmesinin inhibited cytochrome P450 1A2 (CYP1A2) activity in vitro.
Read the full Aegle Marmelos + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with Madhunash Vati Tablets — through 8 ingredients. Tap an ingredient for the detail:
Tinospora CordifoliaCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Tinospora cordifolia might increase levels of drugs metabolized by CYP1A2.
Read the full Tinospora Cordifolia + Acetaminophen, Aspirin interactionAndrographis PaniculataAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, andrographis might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Andrographis Paniculata + Acetaminophen, Aspirin interactionNeemCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP1A2 substrates.
Read the full Neem + Acetaminophen, Aspirin interactionGymnema SylvestreCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP1A2.
Read the full Gymnema Sylvestre + Acetaminophen, Aspirin interactionCurcuma LongaCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Curcuma Longa + Acetaminophen, Aspirin interactionAshwagandhaCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ashwagandha + Acetaminophen, Aspirin interactionTrigonella Foenum-graecumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, fenugreek might have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Trigonella Foenum-graecum + Acetaminophen, Aspirin interactionAegle MarmelosCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Bael extract and its constituent marmesinin inhibited cytochrome P450 1A2 (CYP1A2) activity in vitro.
Read the full Aegle Marmelos + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with Madhunash Vati Tablets — through 8 ingredients. Tap an ingredient for the detail:
Curcuma LongaAnticoagulant/antiplatelet Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +2 Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Curcuma Longa + Acetaminophen, Aspirin, Caffeine interactionTrigonella Foenum-graecumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, fenugreek might have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Trigonella Foenum-graecum + Acetaminophen, Aspirin, Caffeine interactionGymnema SylvestreCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP1A2.
Read the full Gymnema Sylvestre + Acetaminophen, Aspirin, Caffeine interactionAndrographis PaniculataAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, andrographis might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Andrographis Paniculata + Acetaminophen, Aspirin, Caffeine interactionTinospora CordifoliaCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Tinospora cordifolia might increase levels of drugs metabolized by CYP1A2.
Read the full Tinospora Cordifolia + Acetaminophen, Aspirin, Caffeine interactionNeemCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Neem + Acetaminophen, Aspirin, Caffeine interactionAshwagandhaHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Acetaminophen, Aspirin, Caffeine interactionAegle MarmelosCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Bael extract and its constituent marmesinin inhibited cytochrome P450 1A2 (CYP1A2) activity in vitro.
Read the full Aegle Marmelos + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with Madhunash Vati Tablets — through 6 ingredients. Tap an ingredient for the detail:
Curcuma LongaCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Curcuma Longa + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionTinospora CordifoliaCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Tinospora cordifolia might increase levels of drugs metabolized by CYP1A2.
Read the full Tinospora Cordifolia + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionGymnema SylvestreCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP1A2.
Read the full Gymnema Sylvestre + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAshwagandhaHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionNeemCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP1A2 substrates.
Read the full Neem + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAegle MarmelosCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Bael extract and its constituent marmesinin inhibited cytochrome P450 1A2 (CYP1A2) activity in vitro.
Read the full Aegle Marmelos + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, ButalbitalAxocet, Bancap, Bucet, Butex Forte, Esgic CF, Orbivan CF +5 more
How Acetaminophen, Butalbital interacts with Madhunash Vati Tablets — through 6 ingredients. Tap an ingredient for the detail:
NeemCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP1A2 substrates.
Read the full Neem + Acetaminophen, Butalbital interactionTinospora CordifoliaCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Tinospora cordifolia might increase levels of drugs metabolized by CYP1A2.
Read the full Tinospora Cordifolia + Acetaminophen, Butalbital interactionCurcuma LongaHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Curcuma Longa + Acetaminophen, Butalbital interactionAshwagandhaCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ashwagandha + Acetaminophen, Butalbital interactionGymnema SylvestreCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP1A2.
Read the full Gymnema Sylvestre + Acetaminophen, Butalbital interactionAegle MarmelosCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Bael extract and its constituent marmesinin inhibited cytochrome P450 1A2 (CYP1A2) activity in vitro.
Read the full Aegle Marmelos + Acetaminophen, Butalbital interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with Madhunash Vati Tablets — through 6 ingredients. Tap an ingredient for the detail:
Gymnema SylvestreCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP1A2.
Read the full Gymnema Sylvestre + Acetaminophen, Butalbital, Caffeine interactionTinospora CordifoliaCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Tinospora cordifolia might increase levels of drugs metabolized by CYP1A2.
Read the full Tinospora Cordifolia + Acetaminophen, Butalbital, Caffeine interactionCurcuma LongaCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Curcuma Longa + Acetaminophen, Butalbital, Caffeine interactionNeemCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP1A2 substrates.
Read the full Neem + Acetaminophen, Butalbital, Caffeine interactionAshwagandhaHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Acetaminophen, Butalbital, Caffeine interactionAegle MarmelosCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Bael extract and its constituent marmesinin inhibited cytochrome P450 1A2 (CYP1A2) activity in vitro.
Read the full Aegle Marmelos + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with Madhunash Vati Tablets — through 6 ingredients. Tap an ingredient for the detail:
Curcuma LongaHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Curcuma Longa + Acetaminophen, Butalbital, Caffeine, Codeine interactionNeemCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Neem + Acetaminophen, Butalbital, Caffeine, Codeine interactionGymnema SylvestreCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre + Acetaminophen, Butalbital, Caffeine, Codeine interactionTinospora CordifoliaCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, Tinospora cordifolia might increase levels of drugs metabolized by CYP1A2.
Read the full Tinospora Cordifolia + Acetaminophen, Butalbital, Caffeine, Codeine interactionAshwagandhaCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +2 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ashwagandha + Acetaminophen, Butalbital, Caffeine, Codeine interactionAegle MarmelosCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Bael extract and its constituent marmesinin inhibited cytochrome P450 1A2 (CYP1A2) activity in vitro.
Read the full Aegle Marmelos + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with Madhunash Vati Tablets — through 6 ingredients. Tap an ingredient for the detail:
NeemCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP1A2 substrates.
Read the full Neem + Acetaminophen, Butalbital, Codeine interactionGymnema SylvestreCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP1A2.
Read the full Gymnema Sylvestre + Acetaminophen, Butalbital, Codeine interactionAshwagandhaCns Depressants, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Ashwagandha + Acetaminophen, Butalbital, Codeine interactionCurcuma LongaCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Curcuma Longa + Acetaminophen, Butalbital, Codeine interactionTinospora CordifoliaCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Tinospora cordifolia might increase levels of drugs metabolized by CYP2D6.
Read the full Tinospora Cordifolia + Acetaminophen, Butalbital, Codeine interactionAegle MarmelosCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Bael extract and its constituent marmesinin inhibited cytochrome P450 1A2 (CYP1A2) activity in vitro.
Read the full Aegle Marmelos + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with Madhunash Vati Tablets — through 6 ingredients. Tap an ingredient for the detail:
Tinospora CordifoliaCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, Tinospora cordifolia might increase levels of drugs metabolized by CYP1A2.
Read the full Tinospora Cordifolia + Acetaminophen, Butalbital, Codeine Phosphate interactionGymnema SylvestreCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP1A2.
Read the full Gymnema Sylvestre + Acetaminophen, Butalbital, Codeine Phosphate interactionNeemCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP1A2 substrates.
Read the full Neem + Acetaminophen, Butalbital, Codeine Phosphate interactionAshwagandhaCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ashwagandha + Acetaminophen, Butalbital, Codeine Phosphate interactionCurcuma LongaHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Curcuma Longa + Acetaminophen, Butalbital, Codeine Phosphate interactionAegle MarmelosCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Bael extract and its constituent marmesinin inhibited cytochrome P450 1A2 (CYP1A2) activity in vitro.
Read the full Aegle Marmelos + Acetaminophen, Butalbital, Codeine Phosphate interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Madhunash Vati Tablets with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Ashwagandha
Antidiabetes Drugs
Theoretically, taking ashwagandha with antidiabetes drugs might increase the risk of hypoglycemia.
There is preliminary clinical evidence suggesting that ashwagandha might lower blood glucose levels. Theoretically, ashwagandha might have additive effects when used with antidiabetes drugs and increase the risk of hypoglycemia.
Antihypertensive Drugs
Theoretically, taking ashwagandha with antihypertensive drugs might increase the risk of hypotension.
Animal research suggests that ashwagandha might lower systolic and diastolic blood pressure. Theoretically, ashwagandha might have additive effects when used with antihypertensive drugs and increase the risk of hypotension.
Benzodiazepines
Theoretically, taking ashwagandha might increase the sedative effects of benzodiazepines.
There is preliminary evidence that ashwagandha might have an additive effect with diazepam (Valium) and clonazepam (Klonopin). This may also occur with other benzodiazepines.
Cns Depressants
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Ashwagandha seems to have sedative effects. Theoretically, this may potentiate the effects of barbiturates, other sedatives, and anxiolytics.
Hepatotoxic Drugs
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Ashwagandha has been linked to cases of acute hepatitis, liver failure, hepatic encephalopathy, autoimmune hepatitis, the need for liver transplantation, and death due to liver failure.
Immunosuppressants
Theoretically, taking ashwagandha might decrease the effects of immunosuppressants.
Ashwagandha has demonstrated immunostimulant effects in humans. Animal research has shown that ashwagandha can attenuate the immunosuppression caused by cyclophosphamide.
Thyroid Hormone
Ashwagandha might increase the effects and adverse effects of thyroid hormone.
Concomitant use of ashwagandha with thyroid hormones may cause additive therapeutic and adverse effects. Preliminary clinical research and animal studies suggest that ashwagandha boosts thyroid hormone synthesis and secretion. In one clinical study, ashwagandha increased triiodothyronine (T3) and thyroxine (T4) levels by 41.5% and 19.6%, respectively, and reduced serum TSH levels by 17.4% from baseline in adults with subclinical hypothyroidism.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
In vitro research shows that ashwagandha extract induces CYP1A2 enzymes.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
In vitro research shows that ashwagandha extract induces CYP3A4 enzymes.
Serotonergic Drugs
Some animal studies have reported that ashwagandha can enhance serotonergic transmission by altering certain serotonin (5-HT) receptors. However, there is no evidence to suggest that ashwagandha increases the risk of serotonin-related effects, and there have been no published case reports of serotonin syndrome when combined with other serotonergic drugs. Nevertheless, due to the lack of extensive studies on the matter and the fact that ashwagandha appears to affect serotonergic pathways, it would be prudent to exercise caution when combining it with drugs that affect serotonin. [References: - Effects of Withania somnifera (Ashwaga ndha) on Stress and the Stress-Related Neuropsychiatric Disorders Anxiety, Depression, and Insomnia. Curr Neuropharmacol. 2021 Sep 14; 19: 1468–1495. - A Prospective, Randomized Double-Blind, Placebo-Controlled Study of Safety and Efficacy of a High-Concentration Full-Spectrum Extract of Ashwagandha Root in Reducing Stress and Anxiety in Adults. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3573577/]
Curcuma longa
Alkylating Agents
Turmeric has antioxidant effects. Theoretically, this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro research suggests that curcumin, a constituent of turmeric, inhibits mechlorethamine-induced apoptosis of breast cancer cells by up to 70%. Also, animal research shows that curcumin inhibits cyclophosphamide-induced tumor regression. However, some in vitro research shows that curcumin does not affect the apoptosis capacity of etoposide. Also, other laboratory research suggests that curcumin might augment the cytotoxic effects of alkylating agents. Reasons for the discrepancies may relate to the dose of curcumin and the specific chemotherapeutic agent. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effect, if any, turmeric might have on alkylating agents.
Amlodipine (Norvasc)
Taking turmeric with amlodipine may increase levels of amlodipine.
Animal research shows that giving amlodipine 1 mg/kg as a single dose following the use of turmeric extract 200 mg/kg daily for 2 weeks increases the maximum concentration and area under the curve by 53% and 56%, respectively, when compared with amlodipine alone. Additional animal research shows that taking amlodipine 1 mg/kg with a curcumin 2 mg/kg pretreatment for 10 days increases the maximum concentration and area under the curve by about 2-fold when compared with amlodipine alone.
Anticoagulant/Antiplatelet Drugs
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs. However, research is conflicting.
Curcumin, a constituent of turmeric, has demonstrated antiplatelet effects in vitro. Furthermore, two case reports have found that taking turmeric along with warfarin or fluindione was associated with an increased international normalized ratio (INR). However, one clinical study in healthy volunteers shows that taking curcumin 500 mg daily for 3 weeks, alone or with aspirin 100 mg, does not increase antiplatelet effects or bleeding risk. It is possible that the dose of turmeric used in this study was too low to produce a notable effect.
Antidiabetes Drugs
Theoretically, taking turmeric with antidiabetes drugs might increase the risk of hypoglycemia.
Animal research and case reports suggest that curcumin, a turmeric constituent, can reduce blood glucose levels in patients with diabetes. Furthermore, clinical research in adults with type 2 diabetes shows that taking curcumin 475 mg daily for 10 days prior to taking glyburide 5 mg decreased postprandial glucose levels for up to 24 hours when compared with glyburide alone, despite the lack of a significant pharmacokinetic interaction. Other clinical studies in patients with diabetes show that taking curcumin daily can reduce blood glucose levels when compared with placebo.
Antitumor Antibiotics
Turmeric has antioxidant effects. Theoretically, this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro and animal research shows that curcumin, a constituent of turmeric, inhibits doxorubicin-induced apoptosis of breast cancer cells by up to 65%. However, curcumin does not seem to affect the apoptosis capacity of daunorubicin. In fact, some research shows that curcumin might augment the cytotoxic effects of antitumor antibiotics, increasing their effectiveness. Reasons for the discrepancies may relate to the dose of curcumin and the chemotherapeutic agent. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effects, if any, antioxidants such as turmeric have on antitumor antibiotics.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
In vitro and animal research show that turmeric and its constituents curcumin and curcuminoids inhibit CYP3A4. Also, 8 case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking turmeric and cancer medications that are CYP3A4 substrates, including everolimus, ruxolitinib, ibrutinib, and palbociclib, and bortezomib. In another case report, a transplant patient presented with acute nephrotoxicity and elevated tacrolimus levels after consuming turmeric powder at a dose of 15 or more spoonfuls daily for ten days prior. It was thought that turmeric increased levels of tacrolimus due to CYP3A4 inhibition.
Conversely, other in vitro research suggests that turmeric induces CYP3A4 activity, leading to reduced levels of CYP3A4 substrates. An animal model suggests that induction of CYP3A4 occurs after daily curcumin use for 1 week. However, the induction of CYP3A4 by turmeric has not been reported in humans.
Hepatotoxic Drugs
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
There is concern that turmeric might cause hepatotoxicity, especially when highly bioavailable formulations are used in high doses.
Methotrexate (Trexall, Others)
Theoretically, turmeric might have additive effects when used with hepatotoxic drugs such as methotrexate.
In one case report, a 39-year-old female taking methotrexate, turmeric, and linseed oil developed hepatotoxicity.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Theoretically, turmeric might increase blood levels of OATP4C1 substrates.
In vitro research shows that the turmeric constituent curcumin competitively inhibits OATP4C1 transport. This transporter is expressed in the kidney and facilitates the renal excretion of certain drugs. Theoretically, taking turmeric might decrease renal excretion of OATP substrates.
Sulfasalazine (Azulfidine)
Turmeric might increase the effects and adverse effects of sulfasalazine.
Clinical research shows that taking the turmeric constituent, curcumin, can increase blood levels of sulfasalazine by 3.2-fold.
Tacrolimus (Prograf)
Turmeric might increase the effects and adverse effects of tacrolimus.
In one case report, a transplant patient presented with acute nephrotoxicity and elevated tacrolimus levels of 29 ng/mL. The patient previously had tacrolimus levels within the therapeutic range at 9.7 ng/mL. Ten days prior to presenting at the emergency room the patient started consumption of turmeric powder at a dose of 15 or more spoonfuls daily. It was thought that turmeric increased levels of tacrolimus due to cytochrome P450 3A4 (CYP3A4) inhibition. In vitro and animal research show that turmeric and its constituent curcumin inhibit CYP3A4.
Talinolol
Turmeric may reduce the absorption of talinolol in some situations.
Clinical research shows that taking curcumin for 6 days decreases the bioavailability of talinolol when taken together on the seventh day. The clinical significance of this effect is unclear.
Tamoxifen (Nolvadex)
Theoretically, turmeric might reduce the levels and clinical effects of tamoxifen.
In a small clinical trial in patients with breast cancer taking tamoxifen 20-30 mg daily, adding curcumin 1200 mg plus piperine 10 mg three times daily reduces the 24-hour area under the curve of tamoxifen and the active metabolite endoxifen by 12.8% and 12.4%, respectively, as well as the maximum concentrations of tamoxifen, when compared with tamoxifen alone. However, in the absence of piperine, the area under the curve for endoxifen and the maximum concentration of tamoxifen were not significantly reduced. Effects were most pronounced in patients who were extensive cytochrome P450 (CYP) 2D6 metabolizers.
Topoisomerase I Inhibitors
Turmeric has antioxidant effects. There is some concern that this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro research shows that curcumin, a constituent of turmeric, inhibits camptothecin-induced apoptosis of breast cancer cells by up to 71%. However, other in vitro research shows that curcumin augments the cytotoxic effects of camptothecin. Reasons for the discrepancies may relate to the dose of curcumin and the chemotherapeutic agents. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effect, if any, turmeric might have.
Tramadol (Ultram)
Theoretically, turmeric might increase or decrease levels of tramadol.
Animal research suggests that a single dose of curcumin, a constituent of turmeric, may increase tramadol's maximum concentration (Cmax) by inhibiting metabolism, while continued daily use for 7 days may reduce the area under the curve (AUC) due to the induction of drug-metabolizing enzymes such as cytochrome P450 3A4 (CYP3A4). However, this interaction has not been reported in humans.
Warfarin (Coumadin)
Turmeric might increase the risk of bleeding with warfarin.
One case of increased international normalized ratio (INR) has been reported for a patient taking warfarin who began taking turmeric. Prior to taking turmeric, the patient had stable INR measurements. Within a few weeks of starting turmeric supplementation, the patient's INR increased to 10. Additionally, curcumin, the active constituent in turmeric, has demonstrated antiplatelet effects in vitro, which may produce additive effects when taken with warfarin.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2. However, research is conflicting.
In vitro and animal research show that the turmeric constituent, curcumin, inhibits CYP1A2. However, other in vitro research suggests that curcumin does not significantly affect CYP1A2.
Docetaxel (Taxotere)
Theoretically, turmeric might increase blood levels of oral docetaxel.
Animal research suggests that the turmeric constituent, curcumin, enhances the oral bioavailability of docetaxel. However, the significance of this interaction is unclear, as this drug is typically administered intravenously in clinical settings.
Estrogens
Theoretically, large amounts of turmeric might interfere with hormone replacement therapy through competition for estrogen receptors.
In vitro research shows that curcumin, a constituent of turmeric, displaces the binding of estrogen to its receptors.
Glyburide (Diabeta, Others)
Theoretically, taking turmeric and glyburide in combination might increase the risk of hypoglycemia.
Clinical research shows that taking curcumin 475 mg daily for 10 days prior to taking glyburide 5 mg increases blood levels of glyburide by 12% at 2 hours after the dose in patients with type 2 diabetes. While maximal blood concentrations of glyburide were not affected, turmeric modestly decreased postprandial glucose levels for up to 24 hours when compared to glyburide alone, possibly due to the hypoglycemic effect of turmeric demonstrated in animal research.
Losartan (Cozaar)
Theoretically, turmeric might increase the effects of losartan.
Research in hypertensive rats shows that taking turmeric can increase the hypotensive effects of losartan.
Norfloxacin (Noroxin)
Theoretically, turmeric might increase the effects and adverse effects of norfloxacin.
Animal research shows that taking curcumin, a turmeric constituent, can increase blood levels of orally administered norfloxacin.
P-Glycoprotein Substrates
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
In vitro and animal research shows that curcuminoids and other constituents found in turmeric can inhibit P-glycoprotein expression and activity.
Paclitaxel (Abraxane, Onxol)
Theoretically, turmeric might alter blood levels of paclitaxel, although any effect may not be clinically relevant.
Clinical research in adults with breast cancer receiving intravenous paclitaxel suggests that taking turmeric may modestly alter paclitaxel pharmacokinetics. Patients received paclitaxel on day 1, followed by either no treatment or turmeric 2 grams daily from days 2-22. Pharmacokinetic modeling suggests that turmeric reduces the maximum concentration and area under the curve of paclitaxel by 12.1% and 7.7%, respectively. However, these changes are not likely to be considered clinically relevant. Conversely, animal research suggests that curcumin, a constituent of turmeric, enhances the oral bioavailability of paclitaxel. However, the significance of this interaction is unclear, as this drug is typically administered intravenously in clinical settings.
Neem
Antidiabetes Drugs
Neem might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Some clinical research shows that neem can lower blood glucose levels in adults with type 2 diabetes, including those already taking metformin.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP1A2 substrates.
In vitro research shows that neem leaf extract inhibits CYP1A2 enzymes. So far, this reaction has not been reported in humans.
Cytochrome P450 2C8 (Cyp2C8) Substrates
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP2C8 substrates.
In vitro research shows that neem leaf methanol extract inhibits CYP2C8 enzymes. So far, this reaction has not been reported in humans.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP2C9 substrates.
In vitro research shows that neem leaf methanol extract inhibits CYP2C9 enzymes. So far, this reaction has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, neem leaf extract might increase the levels and clinical effects of CYP3A4 substrates.
In vitro research shows that neem leaf methanol extract inhibits CYP3A4 enzymes. So far, this reaction has not been reported in humans.
Immunosuppressants
Theoretically, neem might decrease the effectiveness of immunosuppressants.
Animal research suggests that neem might have immunostimulant effects.
P-Glycoprotein Substrates
Theoretically, neem leaf extract might increase the levels and clinical effects of P-glycoprotein substrates.
In vitro research shows that neem leaf methanol extract inhibits renal P-glycoprotein transport activity. So far, this reaction has not been reported in humans.
Gymnema sylvestre
Antidiabetes Drugs
Theoretically, taking gymnema with antidiabetes drugs might increase the risk of hypoglycemia.
Gymnema reduces blood glucose levels in some human and animal research. In human studies, it has been shown to enhance the blood glucose lowering effects of hypoglycemic drugs. However, other research in adults with prediabetes or metabolic syndrome suggests that gymnema does not reduce fasting levels of blood glucose. Until more is known, monitor blood glucose levels closely.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, gymnema might increase levels of drugs metabolized by CYP1A2.
Animal and in vitro research shows that gymnema can inhibit the CYP1A2 enzyme. In one animal study, oral administration of gymnema for 7 days increased the plasma concentrations of phenacetin, a CYP1A2 substrate, by about 1.4-fold and reduced the clearance of phenacetin by about 29%.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, gymnema might increase or decrease levels of drugs metabolized by CYP2C9.
Animal research shows that gymnema can induce the CYP2C9 enzyme. In one animal study, gymnema caused a 2.4-fold increase in the clearance of tolbutamide, a CYP2C9 substrate, in rats. In vitro research also shows that gymnema can inhibit CYP2C9.
Phenacetin
Theoretically, taking gymnema with phenacetin might increase the levels of phenacetin.
Animal research shows that gymnema, administered orally for 7 days, decreases the clearance of phenacetin in a dose-dependent manner by about 21% to 29% and increases plasma levels about 1.3- to 1.4-fold when compared to control.
Tolbutamide (Orinase)
Theoretically, taking gymnema with tolbutamide might the decrease levels of tolbutamide.
Animal research shows that gymnema, administered orally for 7 days, increases the clearance of tolbutamide by 2.4-fold when compared to control.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
One in vitro study using rat liver microsomes shows that gymnema can modestly inhibit the CYP3A4 enzyme. However, other in vitro research using human liver microsomes shows that gymnema does not affect CYP3A4 activity. Animal research also shows that gymnema does not alter the function of CYP3A4. In one study in rats, oral administration of gymnema for 7 days did not alter the clearance of amlodipine, a CYP3A4 substrate.
Aegle marmelos
Antidiabetes Drugs
Evidence from animal research suggests that extracts of bael seed and leaf can reduce blood glucose levels. Theoretically, bael might have additive effects with antidiabetes drugs and increase the risk of hypoglycemia. Monitor blood glucose levels closely. Dose adjustments might be necessary.
Some antidiabetes drugs include glimepiride (Amaryl), glyburide (DiaBeta, Glynase PresTab, Micronase), insulin, pioglitazone (Actos), rosiglitazone (Avandia), and others.
Cholinergic Drugs
Bael leaf extract shows acetylcholinesterase (AChE) inhibitory activity in vitro. Theoretically, bael might have additive effects with cholinergic drugs and increase the risk of cholinergic side effects.
Cholinergic drugs include bethanechol (Urecholine), donepezil (Aricept), echothiophate (Phospholine Iodide), edrophonium (Enlon, Reversol, Tensilon), neostigmine (Prostigmin), physostigmine (Antilirium), pyridostigmine (Mestinon, Regonol), succinylcholine (Anectine, Quelicin), and tacrine (Cognex).
Cytochrome P450 1A2 (Cyp1A2) Substrates
Bael extract and its constituent marmesinin inhibited cytochrome P450 1A2 (CYP1A2) activity in vitro. So far, this interaction has not been reported in humans. Theoretically, bael might increase levels of drugs metabolized by CYP1A2.
Some drugs metabolized by CYP1A2 include amitriptyline (Elavil), haloperidol (Haldol), ondansetron (Zofran), propranolol (Inderal), theophylline (Theo-Dur, others), verapamil (Calan, Isoptin, others), and others. Use bael cautiously or avoid in patients taking these drugs.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Bael and its constituents marmelosin and marmesinin inhibited cytochrome P450 3A4 (CYP3A4) activity in vitro. So far, this interaction has not been reported in humans. Theoretically, bael might increase levels of drugs metabolized by CYP3A4.
Some drugs metabolized by CYP3A4 include lovastatin (Mevacor), ketoconazole (Nizoral), itraconazole (Sporanox), fexofenadine (Allegra), triazolam (Halcion), and numerous others. Use bael cautiously or avoid in patients taking these drugs.
Tinospora cordifolia
Antidiabetes Drugs
Theoretically, Tinospora cordifolia might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Clinical research in adults with type 2 diabetes shows that Tinospora cordifolia can reduce fasting blood glucose and glycated hemoglobin. Additionally, animal research shows that Tinospora cordifolia has hypoglycemic effects.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, Tinospora cordifolia might increase levels of drugs metabolized by CYP1A2.
In vitro research shows that Tinospora cordifolia extract inhibits CYP1A2 at high concentrations. However, this interaction has not been reported in humans.
Cytochrome P450 2C19 (Cyp2C19) Substrates
Theoretically, Tinospora cordifolia might increase levels of drugs metabolized by CYP2C19.
In vitro research shows that Tinospora cordifolia extract inhibits CYP2C19 at high concentrations. However, this interaction has not been reported in humans.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, Tinospora cordifolia might increase levels of drugs metabolized by CYP2C9.
In vitro research shows that Tinospora cordifolia extract inhibits CYP2C9. Animal research shows that Tinospora cordifolia extract 400 mg/kg twice daily for 14 days reduces the clearance and increases plasma levels of glyburide, a CYP2C9 substrate. However, this interaction has not been reported in humans.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, Tinospora cordifolia might increase levels of drugs metabolized by CYP2D6.
In vitro research shows that Tinospora cordifolia extract inhibits CYP2D6 at high concentrations. However, this interaction has not been reported in humans.
Immunosuppressants
Theoretically, Tinospora cordifolia might reduce the effectiveness of immunosuppressants.
In vitro and animal research shows that Tinospora cordifolia has immunostimulant effects.
Andrographis paniculata
Anticoagulant/Antiplatelet Drugs
Theoretically, andrographis might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Animal and laboratory studies suggest that andrographis has antiplatelet effects.
Antihypertensive Drugs
Theoretically, andrographis might increase the risk of hypotension when used with antihypertensive drugs.
Animal research suggests that andrographis has hypotensive effects.
Immunosuppressants
Theoretically, andrographis might interfere with the effects of immunosuppressive drugs.
Laboratory research suggests that andrographolide has immunostimulant activity.
Celecoxib (Celebrex)
Theoretically, andrographis extract might increase the maximum concentration and time to peak concentration of celecoxib. The clinical significance of these changes is unclear.
Animal research suggests that andrographis extract taken orally increases the maximum concentration and time to peak concentration of celecoxib but does not appear to impact the area under the curve.
Etoricoxib (Arcoxia)
Theoretically, andrographis might decrease the absorption of etoricoxib, although the clinical significance is unclear.
Animal research shows that andrographis extract, or the constituent andrographolide, taken orally with etoricoxib decreases the bioavailability of etoricoxib. However, this reduced bioavailability is not correlated with a reduction in the anti-inflammatory effects of etoricoxib in arthritic mice models. The clinical significance of this interaction is unclear.
Glipizide (Glucotrol)
Theoretically, andrographis extract might increase the maximum concentration and area under the curve of glipizide; however, opposite effects are seen with the constituent, andrographolide. The clinical significance of this interaction is unclear.
Animal research suggests that andrographis extract taken orally with glipizide in diabetes-induced rats increases the maximum concentration and area under the curve of glipizide. However, the opposite effect is seen with the constituent, andrographolide, in which the maximum concentration and area under the curve are decreased when taken with glipizide.
Trigonella foenum-graecum
Anticoagulant/Antiplatelet Drugs
Theoretically, fenugreek might have additive effects when used with anticoagulant or antiplatelet drugs.
Some of the constituents in fenugreek have antiplatelet effects in animal and in vitro research. However, common fenugreek products might not contain sufficient concentrations of these constituents for clinical effects. A clinical study in patients with coronary artery disease or diabetes shows that taking fenugreek seed powder 2.5 grams twice daily for 3 months does not affect platelet aggregation, fibrinolytic activity, or fibrinogen levels .
Antidiabetes Drugs
Theoretically, fenugreek seed might have additive hypoglycemic effects when used with antidiabetes drugs.
Clinical research shows that fenugreek seed can reduce fasting blood glucose and 2-hour postprandial glucose levels in adults with type 2 diabetes.
Clopidogrel (Plavix)
Theoretically, fenugreek seed might alter the clinical effects of clopidogrel by inhibiting its conversion to the active form.
Animal research shows that fenugreek seed 200 mg/kg daily for 14 days increases the maximum serum concentration of clopidogrel by 21%. It is unclear how this affects the pharmacokinetics of the active metabolite of clopidogrel; however, this study found that concomitant use of fenugreek seed and clopidogrel prolonged bleeding time by an additional 11%.
Metoprolol (Toprol)
Theoretically, fenugreek seed might have additive hypotensive effects when used with metoprolol.
Animal research shows that fenugreek seed 300 mg/kg daily for 2 weeks decreases systolic and diastolic blood pressure by 9% and 11%, respectively, when administered alone, and by 15% and 22%, respectively, when given with metoprolol 10 mg/kg.
Phenytoin (Dilantin)
Theoretically, fenugreek might decrease plasma levels of phenytoin.
Animal research shows that taking fenugreek seeds for 1 week decreases maximum concentrations and the area under the curve of a single dose of phenytoin by 44% and 72%, respectively. This seems to be related to increased clearance. So far, this interaction has not been reported in humans.
Sildenafil (Viagra)
Theoretically, concurrent use of sildenafil and fenugreek might reduce levels and therapeutic effects of sildenafil.
Animal research shows that taking fenugreek seeds for 1 week reduces maximum concentrations and the area under the curve of a single dose of sildenafil by 27% and 48%, respectively. So far, this interaction has not been reported in humans.
Theophylline
Theoretically, fenugreek may reduce the levels and clinical effects of theophylline.
Animal research shows that fenugreek 50 grams daily for 7 days reduces the maximum serum concentration (Cmax) of theophylline by 28% and the area under the plasma drug concentration-time curve (AUC) by 22%.
Warfarin (Coumadin)
Theoretically, fenugreek might have additive effects with warfarin and increase the international normalized ratio (INR).
Some fenugreek constituents have antiplatelet effects, although these might not be present in concentrations that are clinically significant. In one case report, a patient taking warfarin experienced an increased INR when starting to take fenugreek in combination with boldo.
Antihypertensive Drugs
Fenugreek may also have an additive effect on blood pressure-lowering medications. Studies on animals have shown that fenugreek seed can decrease both systolic and diastolic blood pressure by up to 22% when combined with metoprolol. Therefore, it is essential to monitor your blood pressure regularly if you are taking fenugreek and metoprolol together or any other antihypertensive drugs.
Momordica charantia
Antidiabetes Drugs
Taking bitter melon with antidiabetes drugs might increase the risk of hypoglycemia.
Bitter melon can lower blood glucose levels and might have additive effects when used with antidiabetes drugs. This might increase the risk of hypoglycemia in some patients. Monitor blood glucose levels closely.
P-Glycoprotein Substrates
Theoretically, bitter melon might increase levels of P-glycoprotein substrates.
Bitter melon might inhibit the p-glycoprotein (P-gp) intestinal pump and increase intracellular levels of P-gp substrates. In vitro research in intestinal cells shows that 1-monopalmitin, a constituent of bitter melon, increases levels of daunomycin, a P-gp substrate. Additionally, drinking bitter melon juice has been associated with a case of acute pancreatitis in a patient who had been taking pazopanib, a P-gp substrate, for 8 years. Researchers theorize that inhibition of P-gp led to increased levels of pazopanib, resulting in pazopanib-induced pancreatitis.
Pazopanib (Votrient)
Theoretically, bitter melon might increase levels of pazopanib, potentially increasing the risk of adverse effects.
In one case, a 65-year-old patient taking pazopanib for 8 years for renal cell carcinoma experienced signs and symptoms consistent with acute pancreatitis 4 days after drinking bitter melon juice at a dose of 100-150 mL daily. The patient's symptoms, amylase levels, and lipase levels improved upon discontinuation of bitter melon and pazopanib. Pazopanib treatment was re-initiated with no further evidence of pancreatitis. Researchers theorize that inhibition of P-glycoprotein by bitter melon led to increased levels of pazopanib, a P-glycoprotein substrate, resulting in pazopanib-induced pancreatitis.
Syzygium cumini
Antidiabetes Drugs
Animal research shows that jambolan seed and bark extracts can lower blood glucose levels. Theoretically, jambolan might have additive effects when used with antidiabetes drugs. This might increase the risk of hypoglycemia in some patients. Monitor blood glucose levels closely.
Cytochrome P450 2C9 (Cyp2C9) Substrates
There is some in vitro evidence that jambolan can inhibit CYP2C9. Theoretically, concomitant use of jambolan with CYP2C9 substrates may increase levels of drugs metabolized by CYP2C9.
Sitagliptin (Januvia)
Animal research shows that jambolan seed extract reduces the sitagliptin maximum plasma concentration and area under the curve by 39% and 22%, respectively. However, blood glucose levels were actually reduced to a greater extent in mice taking jambolan and sitagliptin in combination when compared with either product taken alone. Theoretically, jambolan seed extract might alter the clearance of sitagliptin, although this may not alter the clinical effects of sitagliptin.
Praval pishti
Ceftriaxone (Rocephin)
Co-administration of intravenous calcium and ceftriaxone can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys.
Avoid administering intravenous calcium in any form, such as parenteral nutrition or Lactated Ringers, within 48 hours of intravenous ceftriaxone. Case reports in neonates show that administering intravenous ceftriaxone and calcium can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys. In several cases, neonates have died as a result of this interaction. So far there are no reports in adults; however, there is still concern that this interaction might occur in adults.
Dolutegravir (Tivicay)
Calcium seems to reduce levels of dolutegravir.
Advise patients to take dolutegravir either 2 hours before or 6 hours after taking calcium supplements. Pharmacokinetic research suggests that taking calcium carbonate 1200 mg concomitantly with dolutegravir 50 mg reduces plasma levels of dolutegravir by almost 40%. Calcium appears to decrease levels of dolutegravir through chelation.
Elvitegravir (Vitekta)
Calcium seems to reduce levels of elvitegravir.
Advise patients to take elvitegravir either 2 hours before or 2 hours after taking calcium supplements. Pharmacokinetic research suggests that taking calcium along with elvitegravir can reduce blood levels of elvitegravir through chelation.
Aluminum
Calcium citrate might increase aluminum absorption and toxicity. Other types of calcium do not increase aluminum absorption.
Calcium citrate can increase the absorption of aluminum when taken with aluminum hydroxide. The increase in aluminum levels may become toxic, particularly in individuals with kidney disease. However, the effect of calcium citrate on aluminum absorption is due to the citrate anion rather than calcium cation. Calcium acetate does not appear to increase aluminum absorption.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Calcium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide and calcium can be taken together if taken with food. However, if taken on an empty stomach, bictegravir/emtricitabine/tenofovir alafenamide should not be taken with, or 2 hours after, calcium containing products.
Bisphosphonates
Calcium reduces the absorption of bisphosphonates.
Advise patients to take bisphosphonates at least 30 minutes before calcium, but preferably at a different time of day. Calcium supplements decrease absorption of bisphosphonates.
Calcipotriene (Dovonex)
Taking calcipotriene with calcium might increase the risk for hypercalcemia.
Calcipotriene is a vitamin D analog used topically for psoriasis. It can be absorbed in sufficient amounts to cause systemic effects, including hypercalcemia. Theoretically, combining calcipotriene with calcium supplements might increase the risk of hypercalcemia.
Digoxin (Lanoxin)
Using intravenous calcium with digoxin might increase the risk of fatal cardiac arrhythmias.
Hypercalcemia increases the risk of fatal cardiac arrhythmias with digoxin. However, one retrospective analysis of clinical data suggests that intravenous calcium does not increase the risk of dysrhythmias or mortality in patients receiving digoxin.
Diltiazem (Cardizem, Others)
Theoretically, calcium may reduce the therapeutic effects of diltiazem.
Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically, calcium might increase this risk of hypercalcemia and reduce the effectiveness of diltiazem.
Levothyroxine (Synthroid, Others)
Calcium seems to reduce the absorption and effectiveness of levothyroxine.
Advise patients to take levothyroxine and calcium supplements at least 4 hours apart. Calcium reduces levothyroxine absorption, probably by forming insoluble complexes. Calcium carbonate supplements reduce effectiveness of levothyroxine in patients with hypothyroidism.
Lithium
Theoretically, concomitant use of calcium and lithium may increase this risk of hypercalcemia.
Clinical research suggests that long-term use of lithium may cause hypercalcemia in 10% to 60% of patients. Theoretically, concomitant use of lithium and calcium supplements may further increase this risk.
Quinolone Antibiotics
Calcium seems to reduce the absorption of quinolone antibiotics.
Advise patients to take oral quinolones at least 2 hours before or 4-6 hours after calcium supplements or calcium-fortified foods. Taking calcium at the same time as oral quinolones can reduce quinolone absorption. Calcium binds to quinolones in the gut.
Raltegravir (Isentress)
Calcium may reduce levels of raltegravir.
Pharmacokinetic research shows that taking a single dose of calcium carbonate 3000 mg along with raltegravir 400 mg twice daily modestly decreases the mean area under the curve of raltegravir, but the decrease does not necessitate a dose adjustment of raltegravir. However, a case of elevated HIV-1 RNA levels and documented resistance to raltegravir has been reported for a patient taking calcium carbonate 1 gram three times daily plus vitamin D3 (cholecalciferol) 400 IU three times daily in combination with raltegravir 400 mg twice daily for 11 months. It is thought that calcium reduced raltegravir levels by chelation, leading to treatment failure.
Sotalol (Betapace)
Calcium seems to reduce the absorption of sotalol.
Advise patients to separate doses by at least 2 hours before or 4-6 hours after calcium. Calcium appears to reduce the absorption of sotalol, probably by forming insoluble complexes.
Tetracycline Antibiotics
Calcium seems to reduce the absorption of tetracycline antibiotics.
Advise patients to take oral tetracyclines at least 2 hours before, or 4-6 hours after calcium supplements. Taking calcium at the same time as oral tetracyclines can reduce tetracycline absorption. Calcium binds to tetracyclines in the gut.
Thiazide Diuretics
Taking calcium along with thiazides might increase the risk of hypercalcemia and renal failure.
Thiazides reduce calcium excretion by the kidneys. Using thiazides along with moderately large amounts of calcium carbonate increases the risk of milk-alkali syndrome (hypercalcemia, metabolic alkalosis, renal failure). Patients may need to have their serum calcium levels and/or parathyroid function monitored regularly.
Verapamil (Calan, Others)
Theoretically, calcium may reduce the therapeutic effects of verapamil.
Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically, use of calcium supplements may increase this risk of hypercalcemia and reduce the effectiveness of verapamil.
Calcium Channel Blockers
Intravenous calcium may decrease the effects of calcium channel blockers; oral calcium is unlikely to have this effect.
Intravenous calcium is used to decrease the effects of calcium channel blockers in the management of overdose. Intravenous calcium gluconate has been used before intravenous verapamil (Isoptin) to prevent or reduce the hypotensive effects without affecting the antiarrhythmic effects. But there is no evidence that dietary or supplemental calcium when taken orally interacts with calcium channel blockers.
Shilajit
Antidiabetes Drugs
Taking shilajit with antidiabetes drugs might increase the risk of hypoglycemia.
Most human and animal research shows that shilajit can decrease fasting plasma glucose levels. In an animal model, shilajit 100 mg per kg daily enhanced the glucose-lowering ability of both glibenclamide and metformin when given in combination over a 4 week period. Monitor blood glucose levels closely. Dose adjustments might be necessary.
Swertia chirayita
Antidiabetes Drugs
Theoretically, taking chirata concomitantly with antidiabetes drugs may increase the risk of hypoglycemia.
In non-fasted animals pretreated with the hypoglycemic drug tolbutamide, taking chirata 250 mg/kg decreased blood glucose levels. Monitor blood glucose levels closely.
Brand information
Manufacturer and brand details for Madhunash Vati Tablets, from the product label.
Vedic Supplements
See all Vedic Supplements products- Name
- Sumitra Remedies LLC
- City
- New Brunswick
- State
- NJ
- ZipCode
- 08901
- Phone Number
- 1-612-888-3342
- Web Address
- www.TheVedicStore.com
Madhunash Vati Tablets by Vedic Supplements: Common Questions
Does Madhunash Vati Tablets by Vedic Supplements interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Will this help with my type 2 diabetes?
Can I take this if I'm on blood pressure medication?
Is this safe during pregnancy?
What are the most common side effects?
Does this contain fillers or other inactive ingredients?
Can I take this with my calcium supplement?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Madhunash Vati Tablets is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Madhunash Vati Tablets’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Bael
Interacts with 819 drugsBael is a fruit-bearing tree long used in traditional Indian (Ayurvedic) medicine, mostly for digestive problems like diarrhea and indigestion. Modern human evidence for its medicinal benefi...
Read the full Bael monograph → Herb & supplement monographBitter Melon
Interacts with 282 drugsBitter melon is a tropical fruit eaten as food and used in traditional medicine, most often for blood sugar control. While some small studies hint it may modestly lower blood sugar, the evid...
Read the full Bitter Melon monograph → Herb & supplement monographGymnema
Interacts with 851 drugsGymnema is an Ayurvedic herb best known for possibly helping lower blood sugar and reducing the taste of sweetness on the tongue. Some early human studies are encouraging for blood sugar sup...
Read the full Gymnema monograph → Herb & supplement monographAshwagandha
Interacts with 1,372 drugsAshwagandha is an Ayurvedic herb most often taken to help with stress, anxiety, and sleep, and some small studies suggest it may help, though the evidence is still limited. It is generally w...
Read the full Ashwagandha monograph → Herb & supplement monographNeem
Interacts with 1,013 drugsNeem is a tree from India used for centuries in traditional medicine, especially for skin, dental, and antimicrobial purposes. Some small studies are promising for oral health and skin, but...
Read the full Neem monograph → Herb & supplement monographTinospora Cordifolia
Interacts with 612 drugsTinospora cordifolia, known as Guduchi or Giloy in Ayurvedic medicine, is a climbing plant traditionally used to support immunity and treat fevers. Early laboratory and small human studies s...
Read the full Tinospora Cordifolia monograph → Herb & supplement monographAndrographis
Interacts with 413 drugsAndrographis is a bitter Asian herb traditionally used for colds, flu, and infections, and some studies suggest it may ease cold symptoms and shorten how long they last. The evidence is limi...
Read the full Andrographis monograph → Herb & supplement monographTurmeric
Interacts with 1,133 drugsTurmeric is a popular spice whose main active compounds, curcuminoids, are studied mostly for inflammation and joint pain. Some research is promising, but quality is mixed and curcumin is po...
Read the full Turmeric monograph → Herb & supplement monographFenugreek
Interacts with 389 drugsFenugreek is a common kitchen spice that is also taken as a supplement, mainly for blood sugar, cholesterol, and to support breast milk production. Some early research is encouraging for blo...
Read the full Fenugreek monograph → Herb & supplement monographShilajit
Interacts with 86 drugsShilajit is a sticky, tar-like substance found in rocks of mountain ranges like the Himalayas, used in traditional Ayurvedic medicine for energy and vitality. Human evidence is limited and m...
Read the full Shilajit monograph → Herb & supplement monographJambolan
Interacts with 186 drugsJambolan (Syzygium cumini), also called Java plum or black plum, is a tropical fruit tree traditionally used for blood sugar and digestive complaints. Human evidence for these uses is limite...
Read the full Jambolan monograph → Herb & supplement monographChirata
Interacts with 86 drugsChirata is a very bitter herb used in traditional Ayurvedic and South Asian medicine, mainly for digestion, fever, and as a general tonic. Human evidence for its benefits is limited, so it s...
Read the full Chirata monograph → Herb & supplement monographCalcium
Interacts with 168 drugsCalcium is an essential mineral your body needs for strong bones, nerve signaling, and muscle function, and supplements can help fill gaps when diet falls short. Most people do best getting...
Read the full Calcium monograph →Sources & How We Checked
Madhunash Vati Tablets's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 349 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Bael 7 references
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Sabu, M. C. and Kuttan, R. Antidiabetic activity of Aegle marmelos and its relationship with its antioxidant properties. Indian J Physiol Pharmacol 2004;48(1):81-88.
- Kesari, A. N., Gupta, R. K., Singh, S. K., Diwakar, S., and Watal, G. Hypoglycemic and antihyperglycemic activity of Aegle marmelos seed extract in normal and diabetic rats. J Ethnopharmacol 10-11-2006;107(3):374-379. PubMed
- Haider, R., Khan, A. K., Aziz, K. M., Chowdhury, A., and Kabir, I. Evaluation of indigenous plants in the treatment of acute shigellosis. Trop.Geogr.Med 1991;43(3):266-270.
- Asaduzzaman M, Uddin MJ, Kader MA, et al. In vitro acetylcholinesterase inhibitory activity and the antioxidant properties of Aegle marmelos leaf extract: implications for the treatment of Alzheimer's disease. Psychogeriatrics. 2014;14(1):1-10.
- Yugandhar P, Rao KM, Sengupta K. A novel herbal composition containing extracts of Boswellia serrata gum resin and Aegle marmelos fruit alleviates symptoms of asthma in a placebo controlled double-blind clinical study. Phytother Res. 2018;32(1):140-150.
- Manda VK, Avula B, Chittiboyina AG, Khan IA, Walker LA, Khan SI. Inhibition of CYP3A4 and CYP1A2 by Aegle marmelos and its constituents. Xenobiotica. 2016;46(2):117-25.
Bitter Melon 18 references
- Leatherdale B, Panesar RK, Singh G, et al. Improvement in glucose tolerance due to Momordica charantia. Br Med J (Clin Res Ed) 1981;282:1823-4.
- Welihinda J, et al. Effect of Momordica charantia on the glucose tolerance in maturity onset diabetes. J Ethnopharmacol 1986;17:277-82. PubMed
- Srivastava Y, Venkatakrishna-Bhatt H, Verma Y, et al. Antidiabetic and adaptogenic properties of Momordica charantia extract: An experimental and clinical evaluation. Phytother Res 1993;7:285-9.
- Baldwa VS, Bhandari CM, Pangaria A, Goyal RK. Clinical trial in patients with diabetes mellitus of an insulin-like compound obtained from plant sources. Ups J Med Sci 1977;82:39-41. PubMed
- Aslam M, Stockley IH. Interaction between curry ingredient (karela) and drug (chlorpropamide). Lancet 1979:1:607. PubMed
- Ahmad N, Hassan MR, Halder H, Bennoor KS. Effect of Momordica charantia (Karolla) extracts on fasting and postprandial serum glucose levels in NIDDM patients (abstract). Bangladesh Med Res Counc Bull 1999;25:11-3.
- Basch E, Gabardi S, Ulbricht C. Bitter melon (Momordica charantia): a review of efficacy and safety. Am J Health Syst Pharm 2003;60:356-9. PubMed
- Yin RV, Lee NC, Hirpara H, Phung OJ. T. The effect of bitter melon (Mormordica charantia) in patients with diabetes mellitus: s systematic review and meta-analysis. Nutr Diabetes. 2014;4:e145.
- Rahman IU, Khan RU, Rahman KU, Bashir M. Lower hypoglycemic but higher antiatherogenic effects of bitter melon than glibenclamide in type 2 diabetic patients. Nutr J. 2015;14:13. PubMed
- Alam MA, Uddin R, Subhan N, Rahman MM, Jain P, Reza HM. Beneficial role of bitter melon supplementation in obesity and related complications in metabolic syndrome. J Lipids. 2015;2015:496169. PubMed
- Konishi T, Satsu H, Hatsugai Y, et al. Inhibitory effect of a bitter melon extract on the P-glycoprotein activity in intestinal Caco-2 cells. Br J Pharmacol. 2004;143(3):379-87. PubMed
- Peter EL, Kasali FM, Deyno S, et al. Momordica charantia L. lowers elevated glycaemia in type 2 diabetes mellitus patients: Systematic review and meta-analysis. J Ethnopharmacol. 2019;231:311-24. doi: 10.1016/j.jep.2018.10.033. PubMed
- Cortez-Navarrete M, Martínez-Abundis E, Pérez-Rubio KG, González-Ortiz M, Méndez-Del Villar M. Momordica charantia administration improves insulin secretion in type 2 diabetes mellitus. J Med Food. 2018;21(7):672-7. doi: 10.108
- Kim SK, Jung J, Jung JH, et al. Hypoglycemic efficacy and safety of Momordica charantia (bitter melon) in patients with type 2 diabetes mellitus. Complement Ther Med. 2020 Aug;52:102524. doi: 10.1016/j.ctim.2020.102524. PubMed
- Unsal O, Sütcüoglu O, Yazici O. Dangerous interaction of bitter melon (Momordica charantia) with pazopanib: a case of acute pancreatitis. J Oncol Pharm Pract 2022;28(2):486-8.
- Bae W, Kim S, Choi J, et al. Acute interstitial nephritis associated with ingesting a Momordica charantia extract: a case report. Medicine (Baltimore) 2021;100(27):e26606. PubMed
- Chattopadhyay K, Wang H, Kaur J, et al. Effectiveness and Safety of Ayurvedic Medicines in Type 2 Diabetes Mellitus Management: A Systematic Review and Meta-Analysis. Front Pharmacol. 2022;13:821810. Published 2022 Jun 8. PubMed
- Kim B, Lee HS, Kim HJ, et al. Momordica charantia (bitter melon) efficacy and safety on glucose metabolism in Korean prediabetes participants: a 12-week, randomized clinical study. Food Sci Biotechnol 2022;32(5):697-704. PubMed
Gymnema 12 references
- Shanmugasundaram ER, Rajeswari G, Baskaran K, et al. Use of Gymnema sylvestre leaf extract in the control of blood glucose in insulin-dependent diabetes mellitus. J Ethnopharmacol 1990;30:281-94. PubMed
- Baskaran K, Kizar Ahamath B, Radha Shanmugasundaram K, Shanmugasundaram ER. Antidiabetic effect of leaf extract from Gymnema sylvestre in non-insulin-dependent diabetes mellitus patients. J Ethnopharmacol 1990;30:295-300.
- Kamble B, Gupta A, Moothedath I, Khatal L, Janrao S, Jadhav A, et al. Effects of Gymnema sylvestre extract on the pharmacokinetics and pharmacodynamics of glimepiride in streptozotocin induced diabetic rats. Chem Biol Interact. 2016;245:30-8. PubMed
- Tiwari P, Mishra BN, Sangwan NS. Phytochemical and pharmacological properties of Gymnema sylvestre: an important medicinal plant. Biomed Res Int. 2014; 2014:830285.
- Fabio GD, Romanucci V, De Marco A, Zarrelli A. Triterpenoids from Gymnema sylvestre and their pharmacological activities. Molecules. 2014;19(8):10956-81. PubMed
- Shiyovich A, Sztarkier I, Nesher L. Toxic hepatitis induced by Gymnema sylvestre, a natural remedy for type 2 diabetes mellitus. Am J Med Sci. 2010;340(6):514-7. PubMed
- Zuniga LY, Gonzalez-Ortiz M, Martinez-Abundis E. Effect of gymnema sylvestre administration on metabolic syndrome, insulin sensitivity, and insulin secretion. J Med Food. 2017 Aug;20(8):750-54.
- Rammohan B, Samit K, Chinmoy D, et al. Human cytochrome P450 enzyme modulation by gymnema sylvestre: a predictive safety evaluation by LC-MS/MS. Pharmacogn Mag. 2016 Jul;12(Suppl 4):S389-S394.
- Vaghela M, Sahu N, Kharkar P, Pandita N. In vivo pharmacokinetic interaction by ethanolic extract of gymnema sylvestre with CYP2C9 (tolbutamide), CYP3A4 (amlodipine) and CYP1A2 (phenacetin) in rats. Chem Biol Interact. 2017 Dec 25;278:141-151. PubMed
- Vaghela M, Iyer K, Pandita N. In vitro inhibitory effect of gymnema sylvestre extracts and total gymnemic acids fraction on select cytochrome P450 activities in rat liver microsomes. Eur J Drug Metab Pharmacokinet. 2017 Oct 10. PubMed
- Gaytán Martínez LA, Sánchez-Ruiz LA, Zuñiga LY, González-Ortiz M, Martínez-Abundis E. Effect of Gymnema sylvestre administration on glycemic control, insulin secretion, and insulin sensitivity in patients with impaired glucose tolerance. J Med Food. 2021;
- Philips CA, Theruvath AH, Ravindran R. Toxic hepatitis-associated aplastic anaemia after dual homeopathic remedies and Gymnema sylvestre use. BMJ Case Rep 2022;15(3):e247867. PubMed
Ashwagandha 32 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Upton R, ed. Ashwagandha Root (Withania somnifera): Analytical, quality control, and therapuetic monograph. Santa Cruz, CA: American Herbal Pharmacopoeia 2000:1-25.
- Davis L, Kuttan G. Effect of Withania somnifera on cyclophosphamide-induced urotoxicity. Cancer Lett 2000;148:9-17. PubMed
- Davis L, Kuttan G. Suppressive effect of cyclophosphamide-induced toxicity by Withania somnifera extract in mice. J Ethnopharmacol 1998;62:209-14. PubMed
- Mishra LC, Singh BB, Dagenais S. Scientific basis for the therapeutic use of Withania somnifera (ashwagandha): a review. Altern Med Rev 2000;5:334-46. DOI
- Andallu B, Radhika B. Hypoglycemic, diuretic and hypocholesterolemic effect of winter cherry (Withania somnifera, Dunal) root. Indian J Exp Biol 2000;38:607-9.
- Kulkarni RR, Patki PS, Jog VP, et al. Treatment of osteoarthritis with a herbomineral formulation: a double-blind, placebo-controlled, cross-over study. J Ethnopharmacol 1991;33:91-5. PubMed
- Ahumada F, Aspee F, Wikman G, Hancke J. Withania somnifera exract. Its effects on arterial blood pressure in anaesthetized dogs. Phytother Res 1991;5:111-14.
- Panda S, Kar A. Withania somnifera and Bauhinia purpurea in the regulation of circulating thyroid hormone concentrations in female mice. J Ethnopharmacol 1999;67:233-39. PubMed
- Panda S, Kar A. Changes in thyroid hormone concentrations after administration of ashwagandha root extract to adult male mice. J Pharm Pharmacol 1998;50:1065-68. PubMed
- Sehgal, V. N., Verma, P., and Bhattacharya, S. N. Fixed-drug eruption caused by ashwagandha (Withania somnifera): a widely used Ayurvedic drug. Skinmed. 2012;10(1):48-49.
- Agnihotri AP, Sontakke SD, Thawani VR, Saoji A, Goswami VS. Effects of Withania somnifera in patients of schizophrenia: a randomized, double blind, placebo controlled pilot trial study. Indian J Pharmacol. 2013;45(4):417-8. PubMed
- Biswal BM, Sulaiman SA, Ismail HC, Zakaria H, Musa KI. Effect of Withania somnifera (Ashwagandha) on the development of chemotherapy-induced fatigue and quality of life in breast cancer patients. Integr Cancer Ther. 2013;12(4):312-22.
- Sharma AK, Basu I, Singh S. Efficacy and safety of Ashwagandha root extract in subclinical hypothyroid patients: a double-blind, randomized placebo-controlled trial. J Altern Complement Med. 2018 Mar;24(3):243-248. PubMed
- Durg S, Bavage S, Shivaram SB. Withania somnifera (Indian ginseng) in diabetes mellitus: A systematic review and meta-analysis of scientific evidence from experimental research to clinical application. Phytother Res. 2020;34(5):1041-1059.
- Björnsson HK, Björnsson ES, Avula B, et al. Ashwagandha-induced liver injury: A case series from Iceland and the US Drug-Induced Liver Injury Network. Liver Int. 2020;40(4):825-829. PubMed
- Tharakan A, Shukla H, Benny IR, Tharakan M, George L, Koshy S. Immunomodulatory Effect of Withania somnifera (Ashwagandha) Extract-A Randomized, Double-Blind, Placebo Controlled Trial with an Open Label Extension on Healthy Participants. J Clin Med 2021;1 PubMed
- Ireland PJ, Hardy T, Burt AD, Donnelly MC. Drug-induced hepatocellular injury due to herbal supplement ashwagandha. J R Coll Physicians Edinb. 2021;51(4):363-365. PubMed
- Kamal HI, Patel K, Brdak A, Heffernan J, Ahmad N. Ashwagandha as a unique cause of thyrotoxicosis presenting with supraventricular tachycardia. Cureus. 2022 Mar 25;14(3):e23494. PubMed
- Suryawanshi G, Abdallah M, Thomson M, Desai N, Chauhan A, Lim N. Ashwagandha-Associated Acute Liver Failure Requiring Liver Transplantation. Am J Ther 2023;30(1):e80-e83. PubMed
- Pusec CM, Wolsky R, Llerena C, Sura P. A Case of Supplement-Induced Hepatitis. Cureus 2022;14(10):e30433. PubMed
- Ajgaonkar A, Jain M, Debnath K. Efficacy and Safety of Ashwagandha (Withania somnifera) Root Extract for Improvement of Sexual Health in Healthy Women: A Prospective, Randomized, Placebo-Controlled Study. Cureus 2022;14(10):e30787. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Lubarska M, Halasinski P, Hryhorowicz S, et al. Liver Dangers of Herbal Products: A Case Report of Ashwagandha-Induced Liver Injury. Int J Environ Res Public Health 2023;20(5):3921. PubMed
- Tóth M, Benedek AE, Longerich T, Seitz HK. Ashwagandha-induced acute liver injury: A case report. Clin Case Rep 2023;11(3):e7078.
- Bokan G, Glamocanin T, Mavija Z, et al. Herb-Induced Liver Injury by Ayurvedic Ashwagandha as Assessed for Causality by the Updated RUCAM: An Emerging Cause. Pharmaceuticals (Basel) 2023;16(8):1129. PubMed
- Patel PA, Sanborn E, Then R, Williams DM. Recurrent Reversible Cerebral Vasoconstriction Syndrome: A Report of Two Cases. Cureus 2023;15(8):e42992. PubMed
- Majeed M, Nagabhushanam K, Murali A, Vishwanathan DT, Mamidala RV, Mundkur L. A Standardized Withania somniferra (Linn.) Root Extract with Piperine Alleviates the Symptoms of Anxiety and Depression by Increasing Serotonin Levels: A Double-Blind, Randomize
- Philips CA, Valsan A, Theruvath AH, et al. Ashwagandha-induced liver injury-A case series from India and literature review. Hepatol Commun 2023;7(10):e0270. PubMed
- Hayashi M, Hamada H, Azuma SI, Hayashi K. Painless Thyroiditis by Withania somnifera (Ashwagandha). Cureus 2024;16(3):e55352. PubMed
- Vazirani S, Kothari A, Fujimoto J, Gomez M. Supplements Are Not a Synonym for Safe: Suspected Liver Injury From Ashwagandha. Fed Pract 2023;40(9):315-319. PubMed
- Patel M, Newell R, Hillier M, Ramalingam R. Herbal remedies as a potential cause of hypoadrenalism. Br J Hosp Med (Lond) 2024;85(6):1-4. PubMed
Neem 28 references
- Sinniah D, Baskaran G. Margosa oil poisoning as a cause of Reye's syndrome. Lancet 1981;1:487-9. PubMed
- Sinniah D, Baskaran G, Looi LM, Leong KL. Reye-like syndrome due to margosa oil poisoning: report of a case with postmortem findings. Am J Gastroenterol 1982;77:158-61.
- Sinniah R, Sinniah D, Chia LS, Baskaran G. Animal model of margosa oil ingestion with Reye-like syndrome. Pathogenesis of microvesicular fatty liver. J Pathol 1989;159:255-64. PubMed
- Lai SM, Lim KW, Cheng HK. Margosa oil poisoning as a cause of toxic encephalopathy. Singapore Med J 1990;31:463-5.
- Biswas K, Chattopadhyay I, Banerjee RK, Bandyopadhyay U. Biological activities and medicinal properties of neem (Azadirachta indica). Curr Sci 2002;82:1336-45.
- Upadhyay SN, Dhawan S, Garg S, Talwar GP. Immunomodulatory effects of neem (Azadirachta indica) oil. Int J Immunopharmacol 1992;14:1187-93. PubMed
- Ibrahim IA, Khalid SA, Omer SA, Adam SE. On the toxicology of Azadirachta indica leaves. J Ethnopharmacol 1992;35:267-73. PubMed
- Ali BH. Toxicology of Azadirachta indica. J Ethnopharmacol 1994;42:71-2. PubMed
- Boeke SJ, Boersma MG, Alink GM, et al. Safety evaluation of neem (Azadirachta indica) derived pesticides. J Ethnopharmacol 2004;94:25-41. PubMed
- Abdel-Ghaffar, F. and Semmler, M. Efficacy of neem seed extract shampoo on head lice of naturally infected humans in Egypt. Parasitol.Res 2007;100(2):329-332. PubMed
- Reutemann, P. and Ehrlich, A. Neem oil: an herbal therapy for alopecia causes dermatitis. Dermatitis 2008;19(3):E12-E15.
- Senanayake, M. P., Rupasinghe, S., and Dissanayake, P. V. Margosa (Kohomba) oil induced toxic encephalopathy following home remedy for intestinal worms. Ceylon Med.J 2009;54(4):140. PubMed
- Bhaskar, M. V., Pramod, S. J., Jeevika, M. U., Chandan, P. K., and Shetteppa, G. MR imaging findings of neem oil poisoning. AJNR Am J Neuroradiol. 2010;31(7):E60-E61.
- Iyyadurai, R., Surekha, V., Sathyendra, S., Paul, Wilson B., and Gopinath, K. G. Azadirachtin poisoning: a case report. Clin Toxicol.(Phila) 2010;48(8):857-858. PubMed
- Sinniah, D., Sinniah, R., Baskaran, G., Pathmanathan, R., Yamashita, F., and Yoshino, M. Evaluation of the possible role of glucose, carnitine, coenzyme Q10 and steroids in the treatment of Reye's syndrome using the margosa oil animal model. Acta Paediat PubMed
- Balakrishnan, V., Pillai, N. R., and Santhakumari, G. Ventricular fibrillation and cardiac arrest due to neem leaf poisoning. J.Assoc.Physicians India 1986;34(7):536.
- Sivashanmugham, R., Bhaskar, N., and Banumathi, N. Ventricular fibrillation and cardiac arrest due to neem leaf poisoning. J.Assoc.Physicians India 1984;32(7):610-611.
- Mukherjee, S. and Talwar, G. P. Termination of pregnancy in rodents by oral administration of praneem, a purified neem seed extract. Am J Reprod.Immunol. 1996;35(1):51-56. PubMed
- Talwar, G. P., Pal, R., Singh, O., Garg, S., Taluja, V., Upadhyay, S. N., Gopalan, S., Jain, V., Kaur, J., and Sehgal, S. Safety of intrauterine administration of purified neem seed oil (Praneem Vilci) in women & effect of its co-administration with the
- Talwar, G. P., Shah, S., Mukherjee, S., and Chabra, R. Induced termination of pregnancy by purified extracts of Azadirachta Indica (Neem): mechanisms involved. Am J Reprod.Immunol. 1997;37(6):485-491. PubMed
- Greenblatt DT, Banerjee P, White JM. Allergic contact dermatitis caused by neem oil. Contact Dermatitis. 2012;67(4):242-3. PubMed
- Page C, Hawes EM. Haemolytic anaemia after ingestion of Neem (Azadirachta indica) tea. BMJ Case Rep. 2013. pii: bcr2013200890.
- Braidy N, Berg J, Clement J, et al. Role of nicotinamide dinucleotide and related precursors as therapeutic targets for age-related degenerative diseases: rationale, biochemistry, pharmacokinetics, and outcomes. Antiox Redox Signal 2018.
- Jadhav PB. Leucoderma on the lips induced by neem (Azadirachta indica): case series. Clin Exp Dermatol. 2018;43(8):943-6.
- Giuggioli D, Lumetti F, Spinella A, et al. Use of Neem oil and Hypericum perforatum for treatment of calcinosis-related skin ulcers in systemic sclerosis. J Int Med Res 2019:300060519882176. Online ahead of print.
- Pingali U, Ali MA, Gundagani S, Nutalapati C. Evaluation of the effect of an aqueous extract of Azadirachta indica (neem) leaves and twigs on glycemic control, endothelial dysfunction and systemic inflammation in subjects with type 2 diabetes mellitus - a
- Amaeze O, Marques ES, Wei W, et al. Evaluation of Nigerian Medicinal Plants Extract on Human P-glycoprotein and Cytochrome P450 Enzyme Induction: Implications for Herb-drug Interaction. Curr Drug Metab. 2021;22(14):1103-1113. PubMed
- Amaeze O, Eng H, Horlbogen L, Varma MVS, Slitt A. Cytochrome P450 Enzyme Inhibition and Herb-Drug Interaction Potential of Medicinal Plant Extracts Used for Management of Diabetes in Nigeria. Eur J Drug Metab Pharmacokinet. 2021;46(3):437-450. PubMed
Tinospora Cordifolia 16 references
- Stanely Mainzen Prince P, Menon VP. Hypoglycaemic and hypolipidaemic action of alcohol extract of Tinospora cordifolia roots in chemical induced diabetes in rats. Phytother Res 2003;17:410-3.
- Grover JK, Vats V, Rathi SS. Anti-hyperglycemic effect of Eugenia jambolana and Tinospora cordifolia in experimental diabetes and their effects on key metabolic enzymes involved in carbohydrate metabolism. J Ethnopharmacol 2000;73:461-70. PubMed
- Manjrekar PN, Jolly CI, Narayanan S. Comparative studies of the immunomodulatory activity of Tinospora cordifolia and Tinospora sinensis. Fitoterapia 2000;71:254-7. PubMed
- Prince PS, Menon VP. Antioxidant activity of Tinospora cordifolia roots in experimental diabetes. J Ethnopharmacol 1999;65:277-81. PubMed
- Stanely Mainzen Prince P, Menon VP, Gunasekaran G. Hypolipidaemic action of Tinospora cordifolia roots in alloxan diabetic rats. J Ethnopharmacol 1999;64:53-7. PubMed
- Badar VA, Thawani VR, Wakode PT, et al. Efficacy of Tinospora cordifolia in allergic rhinitis. J Ethnopharmacol 2005;96:445-9. PubMed
- Kapil A, Sharma S. Immunopotentiating compounds from Tinospora cordifolia. J Ethnopharmacol 1997;58:89-95. PubMed
- Nair PK, Rodriguez S, Ramachandran R, et al. Immune stimulating properties of a novel polysaccharide from the medicinal plant Tinospora cordifolia. Int Immunopharmacol 2004;4:1645-59. PubMed
- Castillo AL, Osi MO, Ramos JD, De Francia JL, Dujunco MU, Quilala PF. Efficacy and safety of Tinospora cordifolia lotion in Sarcoptes scabiei var hominis-infected pediatric patients: A single blind, randomized controlled trial. J Pharmacol Pharmacother. 2 PubMed
- Sahu R, Ahmed T, Sangana R, Punde R, Subudhi BB. Effect of Tinospora cordifolia aqua-alcoholic extract on pharmacokinetic of glibenclamide in rat: an herb-drug interaction study. J Pharm Biomed Anal. 2018;151:310-6. doi: 10.1016/j.jpba.2018.01.010. PubMed
- Patial V, Katoch S, Chhimwal J, Singh PP, Suresh PS, Padwad Y. Tinospora cordifolia activates PPAR? pathway and mitigates glomerular and tubular cell injury in diabetic kidney disease. Phytomedicine 2021;91:153663. PubMed
- Kulkarni AV, Hanchanale P, Prakash V, et al. Tinospora Cordifolia (Giloy)-Induced Liver Injury During the COVID-19 Pandemic-Multicenter Nationwide Study From India. Hepatol Commun 2022;6(6):1289-1300. PubMed
- Nagral A, Adhyaru K, Rudra OS, Gharat A, Bhandare S. Herbal Immune Booster-Induced Liver Injury in the COVID-19 Pandemic - A Case Series. J Clin Exp Hepatol. 2021;11(6):732-738. PubMed
- Chattopadhyay K, Wang H, Kaur J, et al. Effectiveness and Safety of Ayurvedic Medicines in Type 2 Diabetes Mellitus Management: A Systematic Review and Meta-Analysis. Front Pharmacol. 2022;13:821810. Published 2022 Jun 8. PubMed
- Nnamani I, Tolu-Akinnawo O, Dufera RR, Akintunde A, Maliakkal B. Tinospora cordifolia (Guduchi/Giloy)-Induced Liver Injury: A Case Review. Cureus 2023;15(5):e39793. PubMed
- May K, Jeitler M, Murthy V, Stapelfeldt E, Kessler CS. A Case Report of Acute Hepatitis Involving the Medicinal Herb Tinospora cordifolia Along with Other Variables. J Integr Complement Med 2023;29(5):327-333.
See these in context on the Tinospora Cordifolia monograph →
Andrographis 26 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Thamlikitkul V, Dechatiwongse T, Theerapong S, et al. Efficacy of Andrographis paniculata, Nees for pharyngotonsillitis in adults. J Med Assoc Thai 1991;74:437-42.
- Zhang CY, Tan BK. Mechanisms of cardiovascular activity of Andrographis paniculata in the anaesthetized rat. J Ethnopharmacol 1997;56:97-101. PubMed
- Zhao HY, Fang WY. Antithrombotic effects of Andrographis paniculata nees in preventing myocardial infarction. Chin Med J (Engl) 1991;104:770-5.
- Amroyan E, Gabrielian E, Panossian A, et al. Inhibitory effect of andrographolide from Andrographis paniculata on PAF-induced platelet aggregation. Phytomedicine 1999;6:27-31. PubMed
- Zhang C, Kuroyangi M, Tan BK. Cardiovascular activity of 14-deoxy-11,12-didehydroandrographolide in the anaesthetised rat and isolated right atria. Pharmacol Res 1998;38:413-7. PubMed
- Puri A, Saxena R, Saxena RP, et al. Immunostimulant agents from Andrographis paniculata. J Nat Prod 1993;56:995-9. PubMed
- Melchoir J, Spasov AA, Ostrovskij OV, et al. Double-blind, placebo-controlled pilot and phase III study of activity of standardized Andrographis paniculata Herba Nees extract fixed combination (Kan Jang) in the treatment of uncomplicated upper-respirator
- Calabrese C, Berman SH, Babish JG, et al. A phase I trial of andrographolide in HIV positive patients and normal volunteers. Phytother Res 2000;14:333-8. PubMed
- Gabrielian ES, Shukarian AK, Goukasova GI, et al. A double blind, placebo-controlled study of Andrographis paniculata fixed combination Kan Jang in the treatment of acute upper respiratory tract infections including sinusitis. Phytomedicine 2002;9:589-97 PubMed
- Poolsup N, Suthisisang C, Prathanturarug S, et al. Andrographis paniculata in the symptomatic treatment of uncomplicated upper respiratory tract infection: systematic review of randomized controlled trials. J Clin Pharm Ther 2004;29:37-45. PubMed
- Coon JT, Ernst E. Andrographis paniculata in the treatment of upper respiratory tract infections: a systematic review of safety and efficacy. Planta Med 2004;70:293-8.
- Kligler, B., Ulbricht, C., Basch, E., Kirkwood, C. D., Abrams, T. R., Miranda, M., Singh Khalsa, K. P., Giles, M., Boon, H., and Woods, J. Andrographis paniculata for the treatment of upper respiratory infection: a systematic review by the natural standa
- Burgos, R. A., Hancke, J. L., Bertoglio, J. C., Aguirre, V., Arriagada, S., Calvo, M., and Caceres, D. D. Efficacy of an Andrographis paniculata composition for the relief of rheumatoid arthritis symptoms: a prospective randomized placebo-controlled tria
- Saxena, R. C., Singh, R., Kumar, P., Yadav, S. C., Negi, M. P., Saxena, V. S., Joshua, A. J., Vijayabalaji, V., Goudar, K. S., Venkateshwarlu, K., and Amit, A. A randomized double blind placebo controlled clinical evaluation of extract of Andrographis pa
- Tang, T., Targan, S. R., Li, Z. S., Xu, C., Byers, V. S., and Sandborn, W. J. Randomised clinical trial: herbal extract HMPL-004 in active ulcerative colitis - a double-blind comparison with sustained release mesalazine. Aliment.Pharmacol Ther 2011;33(2) PubMed
- Sandborn, W. J., Targan, S. R., Byers, V. S., Rutty, D. A., Mu, H., Zhang, X., and Tang, T. Andrographis paniculata extract (HMPL-004) for active ulcerative colitis. Am J Gastroenterol. 2013;108(1):90-98. PubMed
- Melchior, J., Palm, S., and Wikman, G. Controlled clinical study of standardized Andrographis paniculata extract in common cold - a pilot trial. Phytomedicine. 1997;3(4):315-318. PubMed
- Balap A, Atre B, Lohidasan S, et al. Pharmacokinetic and pharmacodynamic herb-drug interaction of Andrographis paniculata (Nees) extract and andrographolide with etoricoxib after oral administration in rats. J Ethnopharmacol. 2016 May 13;183:9-17. PubMed
- Bertoglio JC, Baumgartner M, Palma R, et al. Andrographis paniculata decreases fatigue in patients with relapsing-remitting multiple sclerosis: a 12-month double-blind placebo-controlled pilot study. BMC Neurol. 2016; 16(1):77. PubMed
- Suwankesawong W, Saokaew S, Permsuwan U, et al. Characterization of hypersensitivity reactions reported among Andrographis paniculata users in Thailand using Health Product Vigilance Center (HPVC) database. BMC Complement Altern Med. 2014; 14:515. PubMed
- Ciampi E, Uribe-San-Martin R, Cárcamo C, et al. Efficacy of andrographolide in not active progressive multiple sclerosis: a prospective exploratory double-blind, parallel-group, randomized, placebo-controlled trial. BMC Neurol 2020;20(1):173. PubMed
- Worakunphanich W, Thavorncharoensap M, Youngkong S, Thadanipon K, Thakkinstian A. Safety of Andrographis paniculata: A systematic review and meta-analysis. Pharmacoepidemiol Drug Saf 2021;30(6):727-739.
- More SJ, Tandulwadkar SS, Balap AR, Lohidasan S, Sinnathambi A, Mahadik KR. Effect of Andrographis paniculata extract and Andrographolide on the pharmacokinetics of Aceclofenac and Celecoxib in rats. Futur J Pharm Sci. 2023;9(1):1. PubMed
- Sundhani E, Nugroho AE, Nurrochmad A, Puspitasari I, Amalia Prihati D, Lukitaningsih E. Pharmacokinetic Herb-Drug Interactions of Glipizide with Andrographis paniculata (Burm. f.) and Andrographolide in Normal and Diabetic Rats by Validated HPLC Method. M PubMed
- Shang YX, Shen C, Stub T, et al. Adverse Effects of Andrographolide Derivative Medications Compared to the Safe use of Herbal Preparations of Andrographis paniculata: Results of a Systematic Review and Meta-Analysis of Clinical Studies. Front Pharmacol 20 PubMed
Turmeric 102 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Sharma RA, McLelland HR, Hill KA, et al. Pharmacodynamic and pharmacokinetic study of oral Curcuma extract in patients with colorectal cancer. Clin Cancer Res 2001;7:1894-900..
- Shah BH, Nawaz Z, Pertani SA. Inhibitory effect of curcumin, a food spice from turmeric, on platelet-activating factor- and arachidonic acid-mediated platelet aggregation through inhibition of thromboxane formation and Ca2+ signaling. Biochem Pharmacol 1 PubMed
- Hata M, Sasaki E, Ota M, et al . Allergic contact dermatitis from curcumin (turmeric). Contact Dermatitis 1997;36:107-8. PubMed
- Kuttan R, Sudheeran PC, Josph CD. Turmeric and curcumin as topical agents in cancer therapy. Tumori 1987;73:29-31.. PubMed
- Thapliyal R, Deshpande SS, Maru GB. Mechanism(s) of turmeric-mediated protective effects against benzo(a)pyrene-derived DNA adducts. Cancer Lett 2002;175:79-88. PubMed
- Lee SW, Nah SS, Byon JS, et al. Transient complete atrioventricular block associated with curcumin intake. Int J Cardiol 2011;150:e50-2. PubMed
- Kuptniratsaikul V, Thanakhumtorn S, Chinswangwatanakul P, et al. Efficacy and safety of Curcuma domestica extracts in patients with knee osteoarthritis. J Altern Complement Med 2009;15:891-7.
- Carroll RE, Benya RV, Turgeon DK, et al. Phase IIa clinical trial of curcumin for the prevention of colorectal neoplasia. Cancer Prev Res (Phila) 2011;4:354-64. PubMed
- Junyaprasert, V. B., Soonthornchareonnon, N., Thongpraditchote, S., Murakami, T., and Takano, M. Inhibitory effect of Thai plant extracts on P-glycoprotein mediated efflux. Phytother.Res 2006;20(1):79-81. PubMed
- Ampasavate, C., Sotanaphun, U., Phattanawasin, P., and Piyapolrungroj, N. Effects of Curcuma spp. on P-glycoprotein function. Phytomedicine. 2010;17(7):506-512. PubMed
- Hou, X. L., Takahashi, K., Tanaka, K., Tougou, K., Qiu, F., Komatsu, K., Takahashi, K., and Azuma, J. Curcuma drugs and curcumin regulate the expression and function of P-gp in Caco-2 cells in completely opposite ways. Int.J Pharm 6-24-2008;358(1-2):224-2 PubMed
- Choi, B. H., Kim, C. G., Lim, Y., Shin, S. Y., and Lee, Y. H. Curcumin down-regulates the multidrug-resistance mdr1b gene by inhibiting the PI3K/Akt/NF kappa B pathway. Cancer Lett. 1-18-2008;259(1):111-118.
- Zhang, W., Tan, T. M., and Lim, L. Y. Impact of curcumin-induced changes in P-glycoprotein and CYP3A expression on the pharmacokinetics of peroral celiprolol and midazolam in rats. Drug Metab Dispos. 2007;35(1):110-115. PubMed
- Limtrakul, P., Chearwae, W., Shukla, S., Phisalphong, C., and Ambudkar, S. V. Modulation of function of three ABC drug transporters, P-glycoprotein (ABCB1), mitoxantrone resistance protein (ABCG2) and multidrug resistance protein 1 (ABCC1) by tetrahydrocu
- Holland, M. L., Panetta, J. A., Hoskins, J. M., Bebawy, M., Roufogalis, B. D., Allen, J. D., and Arnold, J. C. The effects of cannabinoids on P-glycoprotein transport and expression in multidrug resistant cells. Biochem.Pharmacol 4-14-2006;71(8):1146-1154 PubMed
- Tang, X. Q., Bi, H., Feng, J. Q., and Cao, J. G. Effect of curcumin on multidrug resistance in resistant human gastric carcinoma cell line SGC7901/VCR. Acta Pharmacol Sin. 2005;26(8):1009-1016. PubMed
- Nabekura, T., Kamiyama, S., and Kitagawa, S. Effects of dietary chemopreventive phytochemicals on P-glycoprotein function. Biochem.Biophys.Res Commun. 2-18-2005;327(3):866-870. PubMed
- Romiti, N., Tongiani, R., Cervelli, F., and Chieli, E. Effects of curcumin on P-glycoprotein in primary cultures of rat hepatocytes. Life Sci. 1998;62(25):2349-2358. PubMed
- Yue, G. G., Cheng, S. W., Yu, H., Xu, Z. S., Lee, J. K., Hon, P. M., Lee, M. Y., Kennelly, E. J., Deng, G., Yeung, S. K., Cassileth, B. R., Fung, K. P., Leung, P. C., and Lau, C. B. The role of turmerones on curcumin transportation and P-glycoprotein acti
- Shenouda, N. S., Zhou, C., Browning, J. D., Ansell, P. J., Sakla, M. S., Lubahn, D. B., and MacDonald, R. S. Phytoestrogens in common herbs regulate prostate cancer cell growth in vitro. Nutr.Cancer 2004;49(2):200-208. PubMed
- Appiah-Opong, R., Commandeur, J. N., Vugt-Lussenburg, B., and Vermeulen, N. P. Inhibition of human recombinant cytochrome P450s by curcumin and curcumin decomposition products. Toxicology 6-3-2007;235(1-2):83-91. PubMed
- Hou, X. L., Takahashi, K., Kinoshita, N., Qiu, F., Tanaka, K., Komatsu, K., Takahashi, K., and Azuma, J. Possible inhibitory mechanism of Curcuma drugs on CYP3A4 in 1alpha,25 dihydroxyvitamin D3 treated Caco-2 cells. Int.J Pharm 6-7-2007;337(1-2):169-177.
- Valentine, S. P., Le Nedelec, M. J., Menzies, A. R., Scandlyn, M. J., Goodin, M. G., and Rosengren, R. J. Curcumin modulates drug metabolizing enzymes in the female Swiss Webster mouse. Life Sci. 4-11-2006;78(20):2391-2398. PubMed
- Price, R. J., Scott, M. P., Giddings, A. M., Walters, D. G., Stierum, R. H., Meredith, C., and Lake, B. G. Effect of butylated hydroxytoluene, curcumin, propyl gallate and thiabendazole on cytochrome P450 forms in cultured human hepatocytes. Xenobiotica 2 PubMed
- Ganta, S., Devalapally, H., and Amiji, M. Curcumin enhances oral bioavailability and anti-tumor therapeutic efficacy of paclitaxel upon administration in nanoemulsion formulation. J Pharm Sci 2010;99(11):4630-4641. PubMed
- Lamb, S. R. and Wilkinson, S. M. Contact allergy to tetrahydrocurcumin. Contact Dermatitis 2003;48(4):227. PubMed
- Joshi, J., Ghaisas, S., Vaidya, A., Vaidya, R., Kamat, D. V., Bhagwat, A. N., and Bhide, S. Early human safety study of turmeric oil (Curcuma longa oil) administered orally in healthy volunteers. J Assoc.Physicians India 2003;51:1055-1060.
- Mahesh, T., Balasubashini, M. S., and Menon, V. P. Effect of photo-irradiated curcumin treatment against oxidative stress in streptozotocin-induced diabetic rats. J Med.Food 2005;8(2):251-255. PubMed
- Thompson, D. A. and Tan, B. B. Tetrahydracurcumin-related allergic contact dermatitis. Contact Dermatitis 2006;55(4):254-255. PubMed
- Patumraj, S., Wongeakin, N., Sridulyakul, P., Jariyapongskul, A., Futrakul, N., and Bunnag, S. Combined effects of curcumin and vitamin C to protect endothelial dysfunction in the iris tissue of STZ-induced diabetic rats. Clin Hemorheol.Microcirc. 2006;3
- Liddle, M., Hull, C., Liu, C., and Powell, D. Contact urticaria from curcumin. Dermatitis 2006;17(4):196-197. PubMed
- Juan, H., Terhaag, B., Cong, Z., Bi-Kui, Z., Rong-Hua, Z., Feng, W., Fen-Li, S., Juan, S., Jing, T., and Wen-Xing, P. Unexpected effect of concomitantly administered curcumin on the pharmacokinetics of talinolol in healthy Chinese volunteers. Eur.J Clin PubMed
- Murugan, P. and Pari, L. Influence of tetrahydrocurcumin on erythrocyte membrane bound enzymes and antioxidant status in experimental type 2 diabetic rats. J Ethnopharmacol. 9-25-2007;113(3):479-486. PubMed
- Seo, K. I., Choi, M. S., Jung, U. J., Kim, H. J., Yeo, J., Jeon, S. M., and Lee, M. K. Effect of curcumin supplementation on blood glucose, plasma insulin, and glucose homeostasis related enzyme activities in diabetic db/db mice. Mol.Nutr.Food Res 2008;5
- Weisberg, S. P., Leibel, R., and Tortoriello, D. V. Dietary curcumin significantly improves obesity-associated inflammation and diabetes in mouse models of diabesity. Endocrinology 2008;149(7):3549-3558. PubMed
- Jain, S. K., Rains, J., Croad, J., Larson, B., and Jones, K. Curcumin supplementation lowers TNF-alpha, IL-6, IL-8, and MCP-1 secretion in high glucose-treated cultured monocytes and blood levels of TNF-alpha, IL-6, MCP-1, glucose, and glycosylated hemog
- Yu, Y., Hu, S. K., and Yan, H. [The study of insulin resistance and leptin resistance on the model of simplicity obesity rats by curcumin]. Zhonghua Yu Fang Yi.Xue.Za Zhi. 2008;42(11):818-822.
- Pavithra, B. H., Prakash, N., and Jayakumar, K. Modification of pharmacokinetics of norfloxacin following oral administration of curcumin in rabbits. J Vet.Sci. 2009;10(4):293-297. PubMed
- Yan, Y. D., Kim, D. H., Sung, J. H., Yong, C. S., and Choi, H. G. Enhanced oral bioavailability of docetaxel in rats by four consecutive days of pre-treatment with curcumin. Int J Pharm 10-31-2010;399(1-2):116-120. PubMed
- Epelbaum, R., Schaffer, M., Vizel, B., Badmaev, V., and Bar-Sela, G. Curcumin and gemcitabine in patients with advanced pancreatic cancer. Nutr Cancer 2010;62(8):1137-1141. PubMed
- Madkor, H. R., Mansour, S. W., and Ramadan, G. Modulatory effects of garlic, ginger, turmeric and their mixture on hyperglycaemia, dyslipidaemia and oxidative stress in streptozotocin-nicotinamide diabetic rats. Br J Nutr 2011;105(8):1210-1217. PubMed
- Pungcharoenkul, K. and Thongnopnua, P. Effect of different curcuminoid supplement dosages on total in vivo antioxidant capacity and cholesterol levels of healthy human subjects. Phytother Res 2011;25(11):1721-1726.
- Kusuhara, H., Furuie, H., Inano, A., Sunagawa, A., Yamada, S., Wu, C., Fukizawa, S., Morimoto, N., Ieiri, I., Morishita, M., Sumita, K., Mayahara, H., Fujita, T., Maeda, K., and Sugiyama, Y. Pharmacokinetic interaction study of sulphasalazine in healthy
- Mohammadi, A., Sahebkar, A., Iranshahi, M., Amini, M., Khojasteh, R., Ghayour-Mobarhan, M., and Ferns, G. A. Effects of supplementation with curcuminoids on dyslipidemia in obese patients: a randomized crossover trial. Phytother Res 2013;27(3):374-379. PubMed
- Chuengsamarn, S., Rattanamongkolgul, S., Luechapudiporn, R., Phisalaphong, C., and Jirawatnotai, S. Curcumin extract for prevention of type 2 diabetes. Diabetes Care 2012;35(11):2121-2127. PubMed
- Goh, C. L. and Ng, S. K. Allergic contact dermatitis to Curcuma longa (turmeric). Contact Dermatitis 1987;17(3):186. PubMed
- Srivastava, R., Puri, V., Srimal, R. C., and Dhawan, B. N. Effect of curcumin on platelet aggregation and vascular prostacyclin synthesis. Arzneimittelforschung. 1986;36(4):715-717.
- Srinivasan, M. Effect of curcumin on blood sugar as seen in a diabetic subject. Indian J Med Sci 1972;26(4):269-270.
- Srivastava, K. C., Bordia, A., and Verma, S. K. Curcumin, a major component of food spice turmeric (Curcuma longa) inhibits aggregation and alters eicosanoid metabolism in human blood platelets. Prostaglandins Leukot.Essent.Fatty Acids 1995;52(4):223-227 PubMed
- Oetari, S., Sudibyo, M., Commandeur, J. N., Samhoedi, R., and Vermeulen, N. P. Effects of curcumin on cytochrome P450 and glutathione S-transferase activities in rat liver. Biochem Pharmacol 1-12-1996;51(1):39-45. PubMed
- Kiec-Swierczynska, M. and Krecisz, B. Occupational allergic contact dermatitis due to curcumin food colour in a pasta factory worker. Contact Dermatitis 1998;39(1):30-31. PubMed
- Van Dau N, Ngoc Ham N, Huy Khac D, and et al. The effects of a traditional drug, tumeric (Curcuma longa), and placebo on the healing of duodenal ulcer. Phytomed 1998;5(1):29-34.
- Daveluy A, Géniaux H, Thibaud L, Mallaret M, Miremont-Salamé G, Haramburu F. Probable interaction between an oral vitamin K antagonist and turmeric (Curcuma longa). Therapie. 2014 Nov-Dec;69(6):519-20. PubMed
- Kuptniratsaikul V, Dajpratham P, Taechaarpornkul W, Buntragulpoontawee M, Lukkanapichonchut P, Chootip C, Saengsuwan J, Tantayakom K, Laongpech S. Efficacy and safety of Curcuma domestica extracts compared with ibuprofen in patients with knee osteoarthrit
- Madhu K, Chanda K, Saji MJ. Safety and efficacy of Curcuma longa extract in the treatment of painful knee osteoarthritis: a randomized placebo-controlled trial. Inflammopharmacology 2013;21(2):129-36. PubMed
- Mali AM, Behal R, Gilda SS. Comparative evaluation of 0.1% turmeric mouthwash with 0.2% chlorhexidine gluconate in prevention of plaque and gingivitis: A clinical and microbiological study. J Indian Soc Periodontol 2012;16(3):386-91. PubMed
- Sanmukhani J, Satodia V, Trivedi J, Patel T, Tiwari D, Panchal B, Goel A, Tripathi CB. Efficacy and safety of curcumin in major depressive disorder: a randomized controlled trial. Phytother Res 2014;28(4):579-85. PubMed
- Nayeri A, Wu S, Adams E, et al. Acute Calcineurin Inhibitor Nephrotoxicity Secondary to Turmeric Intake: A Case Report. Transplant Proc. 2017;49(1):198-200. PubMed
- Mitchell TM. Correspondence re: Somasundaram et al., Dietary curcumin inhibits chemotherapy-induced apoptosis in models of human breast cancer. Cancer Res. 2003;63(16):5165-6; author reply 5166-7.
- Somasundaram S, Edmund NA, Moore DT, Small GW, Shi YY, Orlowski RZ. Dietary curcumin inhibits chemotherapy-induced apoptosis in models of human breast cancer. Cancer Res. 2002;62(13):3868-75.
- Haroyan A, Mukuchyan V, Mkrtchyan N, et al. Efficacy and safety of curcumin and its combination with boswellic acid in osteoarthritis: a comparative, randomized, double-blind, placebo-controlled study. BMC Complement Altern Med. 2018;18(1):7. PubMed
- Al-Karawi D, Al Mamoori DA, Tayyar Y. The role of curcumin administration in patients with major depressive disorder: Mini meta-analysis of clinical trials. Phytother Res. 2016;30(2):175-83. PubMed
- Neerati P, Devde R, Gangi AK. Evaluation of the effect of curcumin capsules on glyburide therapy in patients with type-2 diabetes mellitus. Phytother Res. 2014;28(12):1796-800. PubMed
- Simental-Mendía LE, Pirro M, Gotto AM Jr, et al. Lipid-modifying activity of curcuminoids: A systematic review and meta-analysis of randomized controlled trials. Crit Rev Food Sci Nutr. 2017:1-10. PubMed
- Fung FY, Wong WH, Ang SK, et al. A randomized, double-blind, placebo- controlled study on the anti-haemostatic effects of Curcuma longa, Angelica sinensis and Panax ginseng. Phytomedicine. 2017;32:88-96. PubMed
- Small GW, Siddarth P, Li Z, et al. Memory and brain amyloid and tau effects of a bioavailable form of curcumin in non-demented adults: A double-blind, placebo-controlled 18-month trial. Am J Geriatr Psychiatry. 2018;26(3):266-277.
- Cruz-Correa M, Hylind LM, Marrero JH, et al. Efficacy and safety of curcumin in treatment of intestinal adenomas in patients with familial adenomatous polyposis. Gastroenterology. 2018 May 23. Pii:S0016-5085(18)34564-5. [Epub ahead of print] PubMed
- Rahmani S, Asgary S, Askari G, et al. Treatment of non-alcoholic fatty liver disease with curcumin: a randomized placebo-controlled trial. Phytother Res. 2016 Sep;30(9):1540-8. PubMed
- Lopez-Villafuerte L, CLores KH. Contact dermatitis caused by turmeric in a massage oil. Contact Dermatitis. 2016 Jul;75(1):52-3. PubMed
- Lukefahr AL, McEvoy S, Alfafara C, Funk JL. Drug-induced autoimmune hepatitis associated with turmeric dietary supplement use. BMJ Case Rep. 2018. pii: bcr-2018-224611. PubMed
- Medsafe Safety Communication- Turmeric/Curcumin Interaction with Warfarin. April 30, 2018. Accessed at: https://medsafe.govt.nz/safety/EWS/2018/Turmeric.asp.
- Imam Z, Khasawneh M, Jomaa D, Iftikhar H, Sayedahmad Z. Drug induced liver injury attributed to a curcumin supplement. Case Rep Gastrointest Med 2019 Oct 20;2019:6029403. doi: 10.1155/2019/6029403. PubMed
- Chand S, Hair C, Beswick L. A rare case of turmeric-induced hepatotoxicity. Intern Med J. 2020;50(2):258-259. PubMed
- Jiang N, Zhang M, Meng X, Sun B. Effects of Curcumin on the Pharmacokinetics of Amlodipine in Rats and Its Potential Mechanism. Pharm Biol. 2020;58(1):465-468. PubMed
- Lee BS, Bhatia T, Chaya CT, Wen R, Taira MT, Lim BS. Autoimmune Hepatitis Associated With Turmeric Consumption. ACG Case Rep J. 2020;7(3):e00320. PubMed
- Lombardi N, Crescioli G, Maggini V, et al. Acute liver injury following turmeric use in Tuscany: an analysis of the Italian Phytovigilance database and systematic review of case reports. Br J Clin Pharmacol. 2020. PubMed
- Suhail FK, Masood U, Sharma A, John S, Dhamoon A. Turmeric supplement induced hepatotoxicity: a rare complication of a poorly regulated substance. Clin Toxicol (Phila). 2020;58(3):216-217. PubMed
- Nakagawa Y, Mukai S, Yamada S, et al. The efficacy and safety of highly-bioavailable curcumin for treating knee osteoarthritis: a 6-month open-labeled prospective study. Clin Med Insights Arthritis Musculoskelet Disord. 2020;13:1179544120948471. PubMed
- Shafabakhsh R, Asemi Z, Reiner Z, Soleimani A, Aghadavod E, Bahmani F. The effects of nano-curcumin on metabolic status in patients with diabetes on hemodialysis, a randomized, double blind, placebo-controlled trial. Iran J Kidney Dis. 2020;14(4):290-9.
- Allegri P, Rosa R, Masala A, et al. Clinical effectiveness of a new oral curcumin formulation in acute non-infectious uveitic macular edema: a 12-month observational study. Eur Rev Med Pharmacol Sci 2022;26(1):46-53.
- Tsai IC, Hsu CW, Chang CH, Tseng PT, Chang KV. The effect of curcumin differs on individual cognitive domains across different patient populations: A systematic review and meta-analysis. Pharmaceuticals (Basel) 2021;14(12):1235. PubMed
- Alam MA, Bin Jardan YA, Raish M, Al-Mohizea AM, Ahad A, Al-Jenoobi FI. Herb-drug interaction: Pharmacokinetics and pharmacodynamics of anti-hypertensive drug amlodipine besylate in presence of lepidium sativum and curcuma longa. Xenobiotica 2022;1-9.
- Sohal A, Alhankawi D, Sandhu S, Chintanaboina J. Turmeric-induced hepatotoxicity: Report of 2 cases. Int Med Case Rep J 2021;14:849-852. PubMed
- Hussaarts KGAM, Hurkmans DP, Oomen-de Hoop E, et al. Impact of curcumin (with or without piperine) on the pharmacokinetics of tamoxifen. Cancers (Basel). 2019;11(3):403. PubMed
- Kalluru H, Mallayasamy SR, Kondaveeti SS, Chandrasekhar V, Kalachaveedu M. Effect of turmeric supplementation on the pharmacokinetics of paclitaxel in breast cancer patients: A study with population pharmacokinetics approach. Phytother Res 2022;36(4):1761 PubMed
- 109288 Halegoua-DeMarzio D, Navarro V, Ahmad J, et al. Liver injury associated with turmeric-A growing problem: Ten cases from the drug-induced liver injury network [DILIN]. Am J Med. 2022:S0002-9343(22)00740-9. PubMed
- Arzallus T, Izagirre A, Castiella A, Torrente S, Garmendia M, Zapata EM. Drug induced autoimmune hepatitis after turmeric intake. Gastroenterol Hepatol 2023. PubMed
- Gilad O, Rosner G, Ivancovsky-Wajcman D, et al. Efficacy of wholistic turmeric supplement on adenomatous polyps in patients with familial adenomatous polyposis-A randomized, double-blinded, placebo-controlled study. Genes (Basel) 2022;13(12):2182. PubMed
- Ahad A, Raish M, Abdelrahman IA, et al. Changes in pharmacokinetics and pharmacodynamics of losartan in experimental diseased rats treated with Curcuma longa and Lepidium sativum. Pharmaceuticals (Basel) 2022;16(1):33. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
- Kou H, Huang L, Jin M, He Q, Zhang R, Ma J. Effect of curcumin on rheumatoid arthritis: a systematic review and meta-analysis. Front Immunol 2023;14:1121655. PubMed
- Qiu L, Gao C, Wang H, et al. Effects of dietary polyphenol curcumin supplementation on metabolic, inflammatory, and oxidative stress indices in patients with metabolic syndrome: a systematic review and meta-analysis of randomized controlled trials. Front PubMed
- Sato T, Yagi A, Yamauchi M, et al. The use of an antioxidant enables accurate evaluation of the interaction of curcumin on organic anion-transporting polypeptides 4C1 by preventing auto-oxidation. Int J Mol Sci 2024;25(2):991. PubMed
- Washington O, Robinson E, Simh D, et al. Oxalate nephropathy and chronic turmeric supplementation: a case report. J Bras Nefrol 2024;46(1):99-106. PubMed
- Munshi R, Karande-Patil S, Kumbhar D, Deshmukh A, Hingorani L. A randomized, controlled, comparative, proof-of-concept study to evaluate the efficacy and safety of Nisha-Amalaki capsules in prediabetic patients for preventing progression to diabetes. J Ay PubMed
- Sharifi Razavi A, Mohajerani F, Niksolat F, Karimi N. Efficacy of topical curcumin on mild to moderate carpal tunnel syndrome: a randomized double-blind, placebo-controlled clinical trial. Pain Med 2024;25(5):327-333. PubMed
- Yaikwawong M, Jansarikit L, Jirawatnotai S, Chuengsamarn S. Curcumin Reduces Depression in Obese Patients with Type 2 Diabetes: A Randomized Controlled Trial. Nutrients 2024;16(15):2414. PubMed
- Tehrani SD, Hosseini A, Shahzamani M, et al. Evaluation of the effectiveness of curcumin and piperine co-supplementation on inflammatory factors, cardiac biomarkers, atrial fibrillation, and clinical outcomes after coronary artery bypass graft surgery. Cl PubMed
- Yaikwawong M, Jansarikit L, Jirawatnotai S, Chuengsamarn S. The Effect of Curcumin on Reducing Atherogenic Risks in Obese Patients with Type 2 Diabetes: A Randomized Controlled Trial. Nutrients 2024;16(15):2441. PubMed
- Dibaei M, Hosseini A, Lavasani H, Kiani-Dehkordi B, Rouini M. Assessment of metabolic interaction between curcumin and tramadol using the isolated perfused rat liver. Heliyon 2024;10(15):e35070. PubMed
Fenugreek 30 references
- Madar Z, Thorne R. Dietary fiber. Prog Food Nutr Sci 1987;11:153-74.
- Sharma RD, Raghuram TC, Rao NS. Effect of fenugreek seeds on blood glucose and serum lipids in type I diabetes. Eur J Clin Nutr 1990;44:301-6.
- Patil SP, Niphadkar PV, Bapat MM. Allergy to fenugreek (Trigonella foenum graecum). Ann Allergy Asthma Immunol 1997;78:297-300. PubMed
- Lambert J, Cormier J. Potential interaction between warfarin and boldo-fenugreek. Pharmacotherapy 2001;21:509-12. PubMed
- Bordia A, Verma SK, Srivastava KC. Effect of ginger (Zingiber officinale Rosc.) and fenugreek (Trigonella foenumgraecum L.) on blood lipids, blood sugar and platelet aggregation in patients with coronary artery disease. Prostaglandins Leukot Essent Fatty PubMed
- Yalcin SS, Tekinalp G, Ozalp I. Peculiar odor of traditional food and maple syrup urine disease. Pediatr Int 1999;41:108-9. PubMed
- Sewell AC, Mosandl A, Bohles H. False diagnosis of maple syrup urine disease owing to ingestion of herbal tea. N Engl J Med 1999;341:769.. PubMed
- Abdo MS, al-Kafawi AA. Experimental studies on the effect of Trigonella foenum-graecum (abstract). Planta Med 1969;17:14-8.
- Gupta A, Gupta R, Lal B. Effect of Trigonella foenum-graecum (fenugreek) seeds on glycaemic control and insulin resistance in type 2 diabetes mellitus: a double blind placebo controlled study. J Assoc Physicians India 2001;49:1057-61.
- Gabay MP. Galactogogues: medications that induce lactation. J Hum Lact 2002;18:274-9. PubMed
- Chevassus H, Gaillard JB, Farret A, et al. A fenugreek seed extract selectively reduces spontaneous fat intake in overweight subjects. Eur J Clin Pharmacol 2010;66(5):449-55. PubMed
- Turkyilmaz C, Onal E, Hirfanoglu IM, et al. The effect of galactagogue herbal tea on breast milk production and short-term catch-up of birth weight in the first week of life. J Altern Complement Med 2011;17(2):139-42. PubMed
- Swafford S, Berens P. Effect of fenugreek on breast milk volume. Abstract presented at: 5th International Meeting of the Academy of Breastfeeding Medicine; September 11-13,2000, Tucson, Arizona.
- Abdel-Barry, J. A., Abdel-Hassan, I. A., Jawad, A. M., and al Hakiem, M. H. Hypoglycaemic effect of aqueous extract of the leaves of Trigonella foenum-graecum in healthy volunteers. East Mediterr.Health J 2000;6(1):83-88. DOI
- Parvizpur, A., Ahmadiani, A., and Kamalinejad, M. Probable role of spinal purinoceptors in the analgesic effect of Trigonella foenum (TFG) leaves extract. J Ethnopharmacol 3-8-2006;104(1-2):108-112. PubMed
- Mora, A., Herrrera, A., Lopez, C., Dahbi, G., Mamani, R., Pita, J. M., Alonso, M. P., Llovo, J., Bernardez, M. I., Blanco, J. E., Blanco, M., and Blanco, J. Characteristics of the Shiga-toxin-producing enteroaggregative Escherichia coli O104:H4 German ou
- Blanco, J. [Stx2a-producing enteroaggregative Escherichia coli O104:H4-ST678. Microbiological diagnostic already, for this and other STEC/VTEC serotypes!]. Enferm.Infecc.Microbiol.Clin. 2012;30(2):84-89.
- Beutin, L. and Martin, A. Outbreak of Shiga toxin-producing Escherichia coli (STEC) O104:H4 infection in Germany causes a paradigm shift with regard to human pathogenicity of STEC strains. J Food Prot. 2012;75(2):408-418. PubMed
- King LA, Nogareda F, Weill FX, Mariani-Kurkdjian P, Loukiadis E, Gault G, Jourdan-DaSilva N, Bingen E, Macé M, Thevenot D, Ong N, Castor C, Noël H, Van Cauteren D, Charron M, Vaillant V, Aldabe B, Goulet V, Delmas G, Couturier E, Le Strat Y, Combe C, Delm
- Reeder C, Legrand A, O'Connor-Von SK. The Effect of Fenugreek on Milk Production and Prolactin Levels in Mothers of Preterm Infants. Clinical Lactation 2013;4(4):159-165. DOI
- Al-Jenoobi FI, Ahad A, Mahrous GM, Al-Mohizea AM, AlKharfy KM, Al-Suwayeh SA. Effects of fenugreek, garden cress, and black seed on theophylline pharmacokinetics in beagle dogs. Pharm Biol 2015;53(2):296-300. PubMed
- Rao A, Steels E, Inder WJ, Abraham S, Vitetta L. Testofen, a specialised Trigonella foenum-graecum seed extract reduces age-related symptoms of androgen decrease, increases testosterone levels and improves sexual function in healthy aging males in a doubl
- Steels E, Rao A, Vitetta L. Physiological aspects of male libido enhanced by standardized Trigonella foenum-graecum extract and mineral formulation. Phytother Res. 2011 Sep;25(9):1294-300.
- Gong J, Fang K, Dong H, Wang D, Hu M, Lu F. Effect of fenugreek on hyperglycaemia and hyperlipidemia in diabetes and prediabetes: A meta-analysis. J Ethnopharmacol. 2016 Dec 24;194:260-268. PubMed
- Ouzir M, El Bairi K, Amzazi S. Toxicological properties of fenugreek (Trigonella foenum graecum). Food Chem Toxicol. 2016 Oct;96:145-54. PubMed
- Khodamoradi K, Khosropanah MH, Ayati Z, et al. The Effects of Fenugreek on Cardiometabolic Risk Factors in Adults: A Systematic Review and Meta-analysis. Complement Ther Med. 2020;52:102416. PubMed
- Alkharfy K, Jan B, Alotaibi K, et al. Clopidogrel-herb Interactions: A Pharmacokinetic and Pharmacodynamic Assessment in a Rat Model. Curr Drug Metab 2021;22(12):969-977. PubMed
- Bin Jardan YA, Ahad A, Raish M, Alam MA, Al-Mohizea AM, Al-Jenoobi FI. Effects of garden cress, fenugreek and black seed on the pharmacodynamics of metoprolol: an herb-drug interaction study in rats with hypertension. Pharm Biol 2021;59(1):1088-1097. PubMed
- Al-Mohizea AM, Ahad A, El-Maghraby GM, et al. Effects of Nigella sativa, Lepidium sativum and Trigonella foenum-graecum on sildenafil disposition in beagle dogs. Eur J Drug Metab Pharmacokinet. 2015;40(2):219-24. PubMed
- Alkharfy KM, Al-Jenoobi FI, Al-Mohizea AM, et al. Effects of Lepidium sativum, Nigella sativa and Trigonella foenum-graceum on phenytoin pharmacokinetics in beagle dogs. Phytother Res. 2013;27(12):1800-4.
Shilajit 8 references
- Sadeghi SMH, Hosseini Khameneh SM, Khodadoost M, et al. Efficacy of momiai in tibia fracture repair: A randomized double-blinded placebo-controlled clinical trial. J Altern Complement Med 2020;26(6):521-528.
- Losa F, Deidda M, Firinu D, Martino MLD, Barca MP, Giacco SD. Exercise-induced anaphylaxis with an Ayurvedic drug as cofactor: A case report. World J Clin Cases 2019;7(5):623-627. PubMed
- Biswas TK, Pandit S, Mondal S, et al. Clinical evaluation of spermatogenic activity of processed Shilajit in oligospermia. Andrologia 2010;42(1):48-56. PubMed
- Stavropoulos K, Sotiriadis A, Patoulias D, et al. Pseudohyperaldosteronism due to mumijo consumption during pregnancy: a licorice-like syndrome. Gynecol Endocrinol 2018;34(12):1019-1021. PubMed
- Ghezelbash B, Shahrokhi N, Khaksari M, Ghaderi-Pakdel F, Asadikaram G. Hepatoprotective effects of shilajit on high fat-diet induced non-alcoholic fatty liver disease (NAFLD) in rats. Horm Mol Biol Clin Investig 2020;41(1):/j/hmbci. PubMed
- Ghezelbash B, Shahrokhi N, Khaksari M, Asadikaram G, Shahrokhi M, Shirazpour S. Protective roles of shilajit in modulating resistin, adiponectin, and cytokines in rats with non-alcoholic fatty liver disease. Chin J Integr Med 2022;28(6):531-537. PubMed
- Jafari M, Forootanfar H, Ameri A, et al. Antioxidant, cytotoxic and hyperalgesia-suppressing activity of a native Shilajit obtained from Bahr Aseman mountains. Pak J Pharm Sci 2019;32(5):2167-2173. DOI
- Trivedi NA, Mazumdar B, Bhatt JD, Hemavathi KG. Effect of shilajit on blood glucose and lipid profile in alloxan-induced diabetic rats. Ind. J. Pharmacol. 2004; 36(6):373-376.
Jambolan 7 references
- Teixeira CC, Weinert LS, Barbosa DC, et al. Syzygium cumini (L.) Skeels in the treatment of type 2 diabetes. Diabetes Care 2004;27:3019-20.
- Sharma SB, Nasir A, Prabhu KM, et al. Hypoglycaemic and hypolipidemic effect of ethanolic extract of seeds of Eugenia jambolana in alloxan-induced diabetic rabbits. J Ethnopharmacol 2003;85:201-6. PubMed
- Sridhar SB, Sheetal UD, Pai MR, Shastri MS. Preclinical evaluation of the antidiabetic effect of Eugenia jambolana seed powder in streptozotocin-diabetic rats. Braz J Med Biol Res 2005;38:463-8. PubMed
- Villasenor IM, Lamadrid MR. Comparative anti-hyperglycemic potentials of medicinal plants. J Ethnopharmacol 2006;104:129-31. PubMed
- Chinni S, Dubala A, Kosaraju J, et al. Effect of crude extract of Eugenia jambolana Lam. on human cytochrome P450 enzymes. Phytother Res 2014;28(11):1731-4. doi: 10.1002/ptr.5137.
- Vora A, Varghese A, Kachwala Y, et al. Eugenia jambolana extract reduces the systemic exposure of Sitagliptin and improves conditions associated with diabetes: A pharmacokinetic and a pharmacodynamic herb-drug interaction study. J Tradit Complement Med. 2 PubMed
- Araújo GR, Teles BSBS, Xoteslem GC, Gratieri T, Fortes RC, Novaes MR. Randomized, double-blind clinical trial comparing the healing of stasis ulcers in lower limbs with standard hydrocolloid gel dressings and with dressings with Syzygium cumini extract. P PubMed
Chirata 1 reference
- Sekar, B. C., Mukherjee, B., Chakravarti, R. B., and Mukherjee, S. K. Effect of different fractions of Swertia chirayita on the blood sugar level of albino rats. J.Ethnopharmacol. 1987;21(2):175-181. PubMed
Calcium 62 references
- Shils M, Olson A, Shike M. Modern Nutrition in Health and Disease. 8th ed. Philadelphia, PA: Lea and Febiger, 1994.
- Hernandez-Avila M, Gonzalez-Cossio T, Hernandez-Avila JE, et al. Dietary calcium supplements to lower blood lead levels in lactating women: a randomized placebo-controlled trial. Epidemiology 2003;14:206-12.. PubMed
- Thys-Jacobs S, Ceccarelli S, Bierman A, et al. Calcium supplementation in premenstrual syndrome: a randomized crossover trial. J Gen Intern Med 1989;4:183-9. PubMed
- Maton PN, Burton ME. Antacids revisited: a review of their clinical pharmacology and recommended therapeutic use. Drugs 1999;57:855-70.
- Clemens JD, Feinstein AR. Calcium carbonate and constipation: a historical review of medical mythopoeia. Gastroenterology 1977;72:957-61. DOI
- Saunders D, Sillery J, Chapman R. Effect of calcium carbonate and aluminum hydroxide on human intestinal function. Dig Dis Sci 1988;33:409-13. PubMed
- Friedman PA, Bushinsky DA. Diuretic effects on calcium metabolism. Semin Nephrol 1999;19:551-6.
- Koo WK, Walters JC, Esterlitz J, et al. Maternal calcium supplementation and fetal bone mineralization. Obstet Gynecol 1999;94:577-82. DOI
- Raman L, Rajalakshmi K, Krishnamachari KAVR, et al. Effect of calcium supplementation to undernourished mothers during pregnancy on the bone density of the neonates. Am J Clin Nutr 1978; 31:466-9. DOI
- Murry JJ, Healy MD. Drug-mineral interactions: a new responsibility for the hospital dietician. J Am Diet Assoc 1991;91:66-73.
- Chan JM, Giovannucci E, Andersson SO, et al. Dairy products, calcium, phosphorous, vitamin D, and risk of prostate cancer. Cancer Causes Control 1998;9:559-66.
- Butner LE, Fulco PP, Feldman G, et al. Calcium carbonate-induced hypothyroidism. Ann Intern Med 2000:132:595. PubMed
- Schneyer CR. Calcium carbonate and reduction of levothyroxine efficacy. JAMA 1998;279:750. PubMed
- Moser LR, Smythe MA, Tisdale JE. The use of calcium salts in the prevention and management of verapamil-induced hypotension. Ann Pharmacother 2000;34:622-9. PubMed
- Singh N, Singh PN, Hershman JM. Effect of calcium carbonate on the absorption of levothyroxine. JAMA 2000;283:2822-5. PubMed
- Kahela P, Anttila M, Tikkanen R, Sundquist H. Effect of food, food constituents and fluid volume on the bioavailability of sotalol. Acta Pharmacol Toxicol (Copenh) 1979;44:7-12.. PubMed
- Pletz MW, Petzold P, Allen A, et al. Effect of calcium carbonate on bioavailability of orally administered gemifloxacin. Antimicrob Agents Chemother 2003;47:2158-60.. PubMed
- Bar-Or D, Yoel G. Calcium and calciferol antagonize effect of verapamil in atrial fibrillation. Br Med J 1981;282:1585-6.
- Decktor DL, Robinson M, Maton PN, et al. Effects of aluminum/magnesium hydroxide and calcium carbonate on esophageal and gastric pH in subjects with heartburn. Am J Ther 1995;2:546-52. PubMed
- Simoneau G. Absence of rebound effect with calcium carbonate. Eur J Drug Metab Pharmacokinet 1996;21:351-7. PubMed
- Peters ML, Leonard M, Licata AA. Role of alendronate and risedronate in preventing and treating osteoporosis. Cleve Clin J Med 2001;68:945-51. PubMed
- Bourke JF, Mumford R, Whittaker P, et al. The effects of topical calcipotriol on systemic calcium homeostasis in patients with chronic plaque psoriasis. J Am Acad Dermatol 1997;37:929-34.
- Gueguen L, Pointillart A. The bioavailability of dietary calcium. J Am Coll Nutr 2000;19:119s-136s. PubMed
- Vella A, Gerber TC, Hayes DL, Reeder GS. Digoxin, hypercalcaemia, and cardiac conduction. Postgrad Med J 1999;75:554-6. PubMed
- Bania TC, Blaufeux B, Hughes S, et al. Calcium and digoxin vs. calcium alone for severe verapamil toxicity. Acad Emerg Med 2000;7:1089-96. PubMed
- Tseng M, Breslow RA, Graubard BI, Ziegler RG. Dairy, calcium, and vitamin D intakes and prostate cancer risk in the National Health and Nutrition Examination Epidemiologic Follow-up Study cohort. Am J Clin Nutr 2005;81:1147-54. PubMed
- Weingarten MA, Zalmanovici A, Yaphe J. Dietary calcium supplementation for preventing colorectal cancer and adenomatous polyps. Cochrane Database Syst Rev 2004;(1):CD003548. PubMed
- Tavani A, Bertuccio P, Bosetti C, et al. Dietary intake of calcium, vitamin D, phosphorus and the risk of prostate cancer. Eur Urol 2005;48:27-33. PubMed
- Giovannucci E, Liu Y, Stampfer MJ, Willett WC. A prospective study of calcium intake and incident and fatal prostate cancer. Cancer Epidemiol Biomarkers Prev 2006;15:203-10. PubMed
- Rocephin (ceftriaxone) and calcium interaction. Pharmacist's Letter / Prescriber's Letter 2007;23(10):231005.
- Bolland MJ, Barber PA, Doughty RN, et al. Vascular events in healthy older women receiving calcium supplementation: randomised control trial. BMJ 2008;336:262-6.
- Bolland MJ, Avenell A, Baron JA, et al. Effect of calcium supplements on risk of myocardial infarction and cardiovascular events: meta-analysis. BMJ 2010;341:c3691. PubMed
- Calcium supplementation and vascular events. Pharmacist's Letter / Prescriber's Letter 2008;24(3):240306.
- Dietary reference intakes for calcium and vitamin D. Institute of Medicine, November 30, 2010. Available at: http://www.iom.edu/~/media/Files/Report%20Files/2010/Dietary-Reference-Intakes-for-Calcium-and-Vitamin-D/Vitamin%20D%20and%20Calcium%202010%20Repo
- Coburn JW, Mischel MG, Goodman WG, et al. Calcium citrate markedly enhances aluminum absorption from aluminum hydroxide. Am J Kidney Dis. 1991;17(6):708-11. PubMed
- Bradley JS, Wassel RT, Lee L, et al. Intravenous ceftriaxone and calcium in the neonate: assessing the risk for cardiopulmonary adverse events. Pediatrics. 2009;123(4):e609-13. PubMed
- Kays MB, Overholser BR, Mueller BA, et al. Effects of sevelamer hydrochloride and calcium acetate on the oral bioavailability of ciprofloxacin. Am J Kidney Dis. 2003;42(6):1253-9. PubMed
- Neuhofel, A. L., Wilton, J. H., Victory, J. M., Hejmanowsk, L. G., and Amsden, G. W. Lack of bioequivalence of ciprofloxacin when administered with calcium-fortified orange juice: a new twist on an old interaction. J Clin Pharmacol. 2002;42(4):461-466. DOI
- Dickinson, H. O., Nicolson, D. J., Cook, J. V., Campbell, F., Beyer, F. R., Ford, G. A., and Mason, J. Calcium supplementation for the management of primary hypertension in adults. Cochrane.Database.Syst.Rev. 2006;(2):CD004639. PubMed
- Jones, B. J. and Twomey, P. J. Requesting patterns for serum calcium concentration in patients on long-term lithium therapy. Int J Clin Pract. 2009;63(1):170-172. PubMed
- Levine, M., Nikkanen, H., and Pallin, D. J. The effects of intravenous calcium in patients with digoxin toxicity. J Emerg.Med. 2011;40(1):41-46. PubMed
- Castelo-Branco, C., Ciria-Recasens, M., Cancelo-Hidalgo, M. J., Palacios, S., Haya-Palazuelos, J., Carbonell-Abello, J., Blanch-Rubio, J., Martinez-Zapata, M. J., Manasanch, J., and Perez-Edo, L. Efficacy of ossein-hydroxyapatite complex compared with ca
- Li K, Kaaks R, Linseisen J, Rohrmann S. Associations of dietary calcium intake and calcium supplementation with myocardial infarction and stroke risk and overall cardiovascular mortality in the Heidelberg cohort of the European Prospective Investigation i
- Chung M, Tang AM, Fu Z. Calcium Intake and Cardiovascular Disease Risk: An Updated Systematic Review and Meta-analysis. Ann Intern Med. 2016 Oct 25. PubMed
- Nolan CR, Califano JR, Butzin CA. Influence of calcium acetate or calcium citrate on intestinal aluminum absorption. Kidney Int. 1990;38(5):937-41. PubMed
- Lewis JR, Radavelli-Bagatini S, Rejnmark L, et al. The effects of calcium supplementation on verified coronary heart disease hospitalization and death in postmenopausal women: a collaborative meta-analysis of randomized controlled trials. J Bone Miner Res PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Lappe J, Watson P, Travers-Gustafson D, Recker R, Garland C, Gorham E, Baggerly K, McDonnell SL. Effect of Vitamin D and Calcium Supplementation on Cancer Incidence in Older Women: A Randomized Clinical Trial. JAMA. 2017 Mar 28;317(12):1234-1243. PubMed
- Grove ML, Cook D. Calcium and heart attacks. Doesn't apply to most calcium prescriptions. BMJ. 2010;341:c5003. PubMed
- Insentress [package insert]. Whitehouse Station, NJ: Merck Sharp & Dohme Corp.; 2014.
- Roberts JL, Kiser JJ, Hindman JT, Meditz AL. Virologic failure with a raltegravir-containing antiretroviral regimen and concomitant calcium administration. Pharmacotherapy 2011;31(10):298e-302e. DOI
- Vitekta [package insert]. Foster City, CA: Gilead Sciences, Inc.; 2014.
- Storan ER, O'Gorman SM, Murphy A, Laing M. Case Report of Calciphylaxis Secondary to Calcium and Vitamin D<sub>3</sub> Supplementation. J Cutan Med Surg. 2017;21(2):162-163. DOI
- Jenkins DJA, Spence JD, Giovannucci EL, et al. Supplemental vitamins and minerals for CVD prevention and treatment. J Am Coll Cardiol 2018;71(22):2570-84. PubMed
- Borkenhagen JF, Connor EL, Stafstrom CE. Neonatal hypocalcemic seizures due to excessive maternal calcium ingestion. Pediatr Neurol 2013;48(6):469-71. PubMed
- WHO recommendations on antenatal care for a positive pregnancy experience. Geneva: World Health Organization; 2016 (http://www.who.int/reproductivehealth/publications/maternal_perinatal_health/ anc-positive-pregnancy-experience/en/).
- Aune D, Navarro Rosenblatt DA, Chan DS, et al. Dairy products, calcium, and prostate cancer risk: a systematic review and meta-analysis of cohort studies. Am J Clin Nutr. 2015;101(1):87-117. PubMed
- Lan T, Park Y, Colditz GA, et al. Adolescent dairy product and calcium intake in relation to later prostate cancer risk and mortality in the NIH-AARP Diet and Health Study. Cancer Causes Control. 2020;31(10):891-904. PubMed
- Zhang Y, Li Y, Liu J, et al. Association of Vitamin D or Calcium Supplementation with Cardiovascular Outcomes and Mortality: A Meta-Analysis with Trial Sequential Analysis. J Nutr Health Aging 2021;25(2):263-270. PubMed
- Myung SK, Kim HB, Lee YJ, Choi YJ, Oh SW. Calcium Supplements and Risk of Cardiovascular Disease: A Meta-Analysis of Clinical Trials. Nutrients 2021;13(2):368. PubMed
- Hetaimish B. Neonatal Calcinosis Cutis After Treatment of Hypocalcemia with Calcium Gluconate: A Report of 2 Cases. Am J Case Rep 2024;25:e943397. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC