
Complete Liver Cleanse Ingredients & Drug Interactions
by Nature's Way
What is this page for?
First and foremost: checking Complete Liver Cleanse against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Complete Liver Cleanse is a dietary supplement by Nature's Way with 20 active ingredients. Its ingredients are commonly taken for morning sickness in pregnancy, premenstrual syndrome (pms), preventing or treating b6 deficiency.Based on those ingredients, 1,504 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Turmeric Rhizome, Root Extract, Milk Thistle seed extract, Niacin. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Complete Liver Cleanse by Nature's Way
Ask about any prescription or over-the-counter medication and we check it for interactions with Complete Liver Cleanse by Nature's Way — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Complete Liver Cleanse by Nature's Way
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Partial disclosure
Complete Liver Cleanse contains 20 active ingredients: amino acids (L-glutamine, glycine, L-methionine, and N-acetyl cysteine), B vitamins (thiamine, vitamin B6, folic acid, vitamin B12, niacin, and riboflavin), vitamin C, minerals (calcium D-glucarate and selenium), herbal extracts (milk thistle seed, artichoke leaf, dandelion root, turmeric rhizome, and curcuminoids), taurine, glutathione (Setria), phytosterols, silymarin, and caffeoylquinic acids. The product also contains inactive ingredients: cellulose, hypromellose, magnesium stearate, and silica.
Does it work?
Strong evidence
The evidence behind this product's ingredients is mixed. Within the formula, vitamin B12 is effective for B12 deficiency, calcium is effective for kidney disease and dyspepsia, folic acid is effective for folate deficiency, and thiamine is effective for thiamine deficiency.
Several other ingredients—including vitamin B6, vitamin C, niacin, and L-glutamine—show possible effectiveness for certain conditions (like homocysteine levels, immune support, or liver health), but the strength of that evidence is limited. Most herbal extracts in the blend (dandelion root, silymarin, milk thistle) lack reliable evidence for their claimed uses.
The product itself is marketed as a liver cleanse, but we hold no effectiveness data that directly supports liver 'cleansing' as a clinical outcome.
How safe is it?
Well-documented data
Most ingredients in this formula are generally well tolerated at typical doses. However, several carry important cautions.
Vitamin B6 can harm nerves (peripheral neuropathy) at high doses taken long-term, especially above 1,000 mg daily. Niacin at supplement levels may cause flushing, liver stress, and elevated blood sugar.
N-acetyl cysteine and selenium are safe within normal ranges but can cause problems at excess doses. L-glutamine should be used only under medical supervision in people with kidney or liver disease.
Taurine's long-term safety is less certain. For pregnancy and breastfeeding, most ingredients (L-glutamine, folic acid, vitamin B12, thiamine, calcium, and taurine) are rated likely safe at normal doses, but others lack sufficient safety data—consult your doctor or pharmacist before use during pregnancy or nursing.
Meds to double-check
Major interaction found
Before you take this product, double-check with your pharmacist if you take any of these: nitroglycerin or other heart medications (risk of severe low blood pressure—major concern); blood thinners or antiplatelet drugs like warfarin or aspirin; seizure medications such as phenytoin or phenobarbital; HIV integrase inhibitors like dolutegravir or elvitegravir; cephalosporin antibiotics like ceftriaxone; diabetes drugs; blood pressure medication; kidney medication (lithium); or quinolone antibiotics like ciprofloxacin. No interactions are documented for the ingredients we could not check (curcuminoids, phytosterols, silymarin, and caffeoylquinic acids).
The bottom line
Scorecard at a glancePartially disclosed formula with clinical evidence supporting its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
This product may appeal to anyone wanting broad nutritional support with amino acids and B vitamins, but its liver-cleansing claims lack established evidence. If you take heart medications (especially nitroglycerin), blood thinners, seizure drugs, HIV medications, or certain antibiotics, talk to your pharmacist or doctor before starting—the interaction risks are real.
Even without those medications, check your full medication list with a pharmacist, because the ingredient count makes drug interactions a genuine concern.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 17 of 20 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated May 21, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Complete Liver Cleanse, straight from the product label.
| Brand | Nature's Way |
|---|---|
| Barcode (UPC) | 763948013159 |
| Net contents | 84 Capsule(s) |
| Market status | On market |
| Date entered into DSLD | May 21, 2025 |
| DSLD ID | 327919 |
| Product type | Other Combinations |
| Supplement form | Capsule |
| Dietary claims / uses | Nutrient, All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Dairy Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for Complete Liver Cleanse by Nature's Way, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Total Carbohydrates | 1 Gram(s) | 1% |
| L-Glutamine | 0 NP | -- |
| Vitamin B6 | 10 mg | 588% |
| Folic Acid | 200 mcg | -- |
| Vitamin B12 | 42 mcg | 1750% |
| Glycine | 0 NP | -- |
| Riboflavin | 8.3 mg | 638% |
| Vitamin C | 50 mg | 56% |
| Niacin | 10 mg | 63% |
| Folate | 333 mcg DFE | 83% |
| Selenium | 66 mcg | 120% |
| Taurine | 0 NP | -- |
| Curcuminoids | 47.5 mg | -- |
| Calcium D-Glucarate | 100 mg | -- |
| Milk Thistle seed extract | 265 mg | -- |
| Artichoke leaf extract | 30 mg | -- |
| Dandelion Root Extract | 50 mg | -- |
| Phytosterols | 200 mg | -- |
| Thiamine | 8.7 mg | 725% |
| Silymarin | 132.5 mg | -- |
| N-Acetyl L-Cysteine | 0 NP | -- |
| Setria | 125 mg | -- |
| Turmeric Rhizome, Root Extract | 50 mg | -- |
| L-Methionine | 0 NP | -- |
| Amino Acid Liver Blend | 330 mg | -- |
| Caffeoylquinic Acids | 3.9 mg | -- |
Other ingredients: Cellulose, Hypromellose, Magnesium Stearate, Silica
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formulation
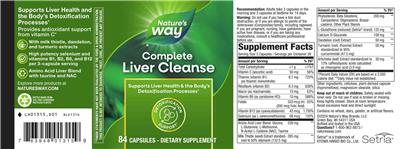
Supports liver health and the body's detoxification processes Provides antioxidant support from Vitamin C
Supports liver health & the body's detoxification processes Detoxification support
Contains no wheat, dairy, gelatin, or artificial flavors.
Bottled and tested in the USA
Formula
Complete Liver Cleanse With milk thistle, dandelion, and turmeric extracts High potency selenium and Vitamins B1, B2, B6, and B12 per 3-capsule serving Amino Acid Liver Blend with taurine and NAC
General Statements
Explore more products at naturesway.com Bottle made from 50% post-consumer recycled plastic
FDA Disclaimer Statement
These statements have not been evaluated by the Food & Drug Administration. This product is not intended to diagnose, treat, cure, or prevent any disease.
FDA Statement of Identity
Dietary Supplement
Suggested/Recommended/Usage/Directions
Recommendation: Adults take 3 capsules in the morning and 3 capsules at bedtime for 14 days.
Precautions
Warning: Do not use if you have a bile duct obstruction, or if you are allergic to plants of the Asteraceae (Compositae) family, including ragweed.
If you are pregnant, nursing, have gallstones, have active liver disease or if you are taking any medications, consult a healthcare professional before use.
Keep out of reach of children.
Safety sealed with inner seal. Do not use if seal is broken or missing.
Storage
Keep tightly closed. Store at room temperatures. Avoid excessive heat and direct sunlight.
Brand IP Statement(s)
Copyright 2024 Nature's Way Brands, LLC
Setria is a trademark of Kyowa Hakko Bio Co., Ltd.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Complete Liver Cleanse by Nature's Way label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Complete Liver Cleanse by Nature's Way
These are the 20 active ingredients this product is made of. Select any to open its full monograph.
Serving size3 Capsule(s) Dosage formCapsule Servings per container28 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Vitamin B6
Interacts with210 drugs
Vitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is b...
Vitamin B6 monograph & interactionsVitamin B12
Interacts with20 drugs
Vitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very h...
Vitamin B12 monograph & interactionsRiboflavin
Interacts with20 drugs
Riboflavin (vitamin B2) is an essential nutrient your body needs to turn food into energy and to keep skin, eyes, and nerves healthy. It is generally...
Riboflavin monograph & interactionsVitamin C
Interacts with207 drugs
Vitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for im...
Vitamin C monograph & interactionsNiacin
Interacts with727 drugs
Niacin (vitamin B3) is an essential nutrient your body needs for energy and metabolism, and deficiency is uncommon in most developed countries. Prescr...
Niacin monograph & interactionsFolate
Selenium
Interacts with321 drugs
Selenium is an essential trace mineral your body needs in small amounts for thyroid function, antioxidant defense, and immune health. Most people who...
Selenium monograph & interactionsCalcium D-Glucarate
Interacts with168 drugs
Calcium is an essential mineral your body needs for strong bones, nerve signaling, and muscle function, and supplements can help fill gaps when diet f...
Calcium D-Glucarate monograph & interactionsMilk Thistle seed extract
Interacts with954 drugs
Milk thistle is a popular herbal supplement most often used for liver health, and its main active component is a group of compounds called silymarin....
Milk Thistle seed extract monograph & interactions- › Silymarin
Artichoke leaf extract
Interacts with363 drugs
Artichoke leaf extract is a generally well-tolerated supplement that may have a mild cholesterol-lowering effect and is often used for indigestion, th...
Artichoke leaf extract monograph & interactions- › Caffeoylquinic Acids
Dandelion Root Extract
Interacts with457 drugs
Dandelion is a common plant used in food and traditional medicine, often promoted as a natural 'water pill' and digestive aid. Human evidence for thes...
Dandelion Root Extract monograph & interactionsPhytosterols
Thiamine
Interacts with3 drugs
Thiamine (vitamin B1) is an essential nutrient your body needs to turn food into energy and to keep your nerves and heart healthy. Most people get eno...
Thiamine monograph & interactionsSetria
No knowninteractions
Glutathione is a powerful antioxidant your body makes naturally, and many people take it as a supplement hoping for skin, detox, or anti-aging benefit...
Setria monograph & interactionsTurmeric Rhizome, Root Extract
Interacts with1,133 drugs
Turmeric is a popular spice whose main active compounds, curcuminoids, are studied mostly for inflammation and joint pain. Some research is promising,...
Turmeric Rhizome, Root Extract monograph & interactionsAmino Acid Liver Blend
- › L-Glutamine
- › Glycine
- › Taurine
- › N-Acetyl L-Cysteine
- › L-Methionine
Other (inactive) ingredients: Cellulose, Hypromellose, Magnesium Stearate, Silica. These complete the product’s ingredient list but are not active constituents.
Complete Liver Cleanse by Nature's Way Drug Interactions
HelloPharmacist Interaction Report
Complete Liver Cleanse by Nature's Way contains 20 ingredients, several of which interact with medications.
The most serious interaction is with N-acetyl cysteine and nitroglycerin (a heart medication): together they can cause severe low blood pressure (hypotension) and dangerous headaches. If you take nitroglycerin patches or spray, this product isn't for you.
Read the full breakdown — every affected drug type, severity by severity
Several ingredients affect blood thinners and antiplatelet drugs (such as warfarin, aspirin, and newer anticoagulants). Vitamin C, selenium, dandelion root, and N-acetyl cysteine all carry documented interactions here.
Vitamin B6 and folic acid interact with seizure medications—they may reduce how well those drugs work. Niacin and taurine may lower blood pressure further if you're already on blood pressure medication.
Dandelion root and L-glutamine also interact with diabetes drugs, and dandelion root can interfere with certain antibiotics (quinolones) and with kidney medication (lithium).
Calcium D-glucarate stands out for major interactions with HIV integrase inhibitors (dolutegravir and elvitegravir) and ceftriaxone, a powerful antibiotic—the product may significantly reduce how well those drugs work. We could not check curcuminoids, phytosterols, or silymarin, so we hold no interaction data for those ingredients.
Altogether, these interactions span 1,078 individual medications. Before you start this product, run your exact medications through the search tool on this page.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Complete Liver Cleanse?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Complete Liver Cleanse interact with 1,504 drugs. Click any drug to see the details.
17 of the 20 ingredients in Complete Liver Cleanse interact with drugs. Each result below shows which ingredient is responsible. Turmeric Rhizome, Root Extract Milk Thistle seed extract Niacin Dandelion Root Extract Artichoke leaf extract Selenium N-Acetyl L-Cysteine Vitamin B6 Vitamin C Taurine Calcium D-Glucarate L-Glutamine Folic Acid Vitamin B12 Riboflavin Thiamine Glycine
CeftriaxoneRocephin
How Ceftriaxone interacts with Complete Liver Cleanse — through 1 ingredient. Tap an ingredient for the detail:
Calcium D-glucarateCeftriaxone (rocephin) Major
Interaction Summary
Co-administration of intravenous calcium and ceftriaxone can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys.
Read the full Calcium D-glucarate + Ceftriaxone interactionCobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide FumarateGenvoya
How Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interacts with Complete Liver Cleanse — through 4 ingredients. Tap an ingredient for the detail:
Calcium D-glucarateBictegravir/emtricitabine/tenofovir Alafenamide (biktarvy), Elvitegravir (vitekta) Major
Interaction Summary
Calcium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Read the full Calcium D-glucarate + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionTurmeric Rhizome, Root ExtractP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
Read the full Turmeric Rhizome, Root Extract + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionMilk Thistle Seed ExtractP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, milk thistle might increase the absorption of P-glycoprotein substrates.
Read the full Milk Thistle Seed Extract + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionDolutegravirTivicay
How Dolutegravir interacts with Complete Liver Cleanse — through 4 ingredients. Tap an ingredient for the detail:
Calcium D-glucarateDolutegravir (tivicay) Major
Interaction Summary
Calcium seems to reduce levels of dolutegravir.
Read the full Calcium D-glucarate + Dolutegravir interactionMilk Thistle Seed ExtractP-glycoprotein Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might increase the absorption of P-glycoprotein substrates.
Read the full Milk Thistle Seed Extract + Dolutegravir interactionDandelion Root ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Dolutegravir interactionTurmeric Rhizome, Root ExtractP-glycoprotein Substrates Minor
Interaction Summary
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
Read the full Turmeric Rhizome, Root Extract + Dolutegravir interactionDolutegravir, Emtricitabine, Tenofovir AlafenamideDolutegravir, Emtricitabine, Tenofovir Alafenamide
How Dolutegravir, Emtricitabine, Tenofovir Alafenamide interacts with Complete Liver Cleanse — through 5 ingredients. Tap an ingredient for the detail:
Calcium D-glucarateDolutegravir (tivicay), Bictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Major
Interaction Summary
Calcium seems to reduce levels of dolutegravir.
Read the full Calcium D-glucarate + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionDandelion Root ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionMilk Thistle Seed ExtractGlucuronidated Drugs, P-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionTurmeric Rhizome, Root ExtractP-glycoprotein Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
Read the full Turmeric Rhizome, Root Extract + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionDolutegravir, RilpivirineJuluca
How Dolutegravir, Rilpivirine interacts with Complete Liver Cleanse — through 4 ingredients. Tap an ingredient for the detail:
Calcium D-glucarateDolutegravir (tivicay) Major
Interaction Summary
Calcium seems to reduce levels of dolutegravir.
Read the full Calcium D-glucarate + Dolutegravir, Rilpivirine interactionMilk Thistle Seed ExtractP-glycoprotein Substrates, Glucuronidated Drugs +1 Moderate
Interaction Summary
Theoretically, milk thistle might increase the absorption of P-glycoprotein substrates.
Read the full Milk Thistle Seed Extract + Dolutegravir, Rilpivirine interactionDandelion Root ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Dolutegravir, Rilpivirine interactionTurmeric Rhizome, Root ExtractP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
Read the full Turmeric Rhizome, Root Extract + Dolutegravir, Rilpivirine interactionElvitegravirVitekta
How Elvitegravir interacts with Complete Liver Cleanse — through 3 ingredients. Tap an ingredient for the detail:
Calcium D-glucarateElvitegravir (vitekta) Major
Interaction Summary
Calcium seems to reduce levels of elvitegravir.
Read the full Calcium D-glucarate + Elvitegravir interactionTurmeric Rhizome, Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Rhizome, Root Extract + Elvitegravir interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Elvitegravir interactionElvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil FumarateStribild
How Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interacts with Complete Liver Cleanse — through 4 ingredients. Tap an ingredient for the detail:
Calcium D-glucarateElvitegravir (vitekta), Bictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Major
Interaction Summary
Calcium seems to reduce levels of elvitegravir.
Read the full Calcium D-glucarate + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionTurmeric Rhizome, Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Rhizome, Root Extract + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionNitroglycerinGonitro, Nitro Time, Nitro-Bid, Nitrocine Timecaps, Nitrogard, Nitrogard SR +7 more
How Nitroglycerin interacts with Complete Liver Cleanse — through 1 ingredient. Tap an ingredient for the detail:
N-acetyl L-cysteineNitroglycerin Major
Interaction Summary
N-acetyl cysteine can increase the risk for hypotension and headaches when taken with intravenous or transdermal nitroglycerin.
Read the full N-acetyl L-cysteine + Nitroglycerin interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with Complete Liver Cleanse — through 3 ingredients. Tap an ingredient for the detail:
SeleniumImmunosuppressants Moderate
Interaction Summary
Theoretically, selenium supplementation may reduce the effectiveness of immunosuppressant therapy.
Read the full Selenium + 6-mercaptopurine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + 6-mercaptopurine interactionTurmeric Rhizome, Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Rhizome, Root Extract + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with Complete Liver Cleanse — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Rhizome, Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Rhizome, Root Extract + Ado-trastuzumab Emtansine interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with Complete Liver Cleanse — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Rhizome, Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Rhizome, Root Extract + Abacavir Sulfate, Dolutegravir, Lamivudine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with Complete Liver Cleanse — through 2 ingredients. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Abacavir, Lamivudine interactionTurmeric Rhizome, Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Rhizome, Root Extract + Abacavir, Lamivudine interactionAbciximabReoPro
How Abciximab interacts with Complete Liver Cleanse — through 5 ingredients. Tap an ingredient for the detail:
SeleniumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Selenium + Abciximab interactionNiacinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Niacin + Abciximab interactionN-acetyl L-cysteineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, N-acetyl cysteine might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full N-acetyl L-cysteine + Abciximab interactionTurmeric Rhizome, Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Rhizome, Root Extract + Abciximab interactionDandelion Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
Read the full Dandelion Root Extract + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with Complete Liver Cleanse — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Rhizome, Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Rhizome, Root Extract + Abemaciclib interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Abemaciclib interactionAbiraterone
How Abiraterone interacts with Complete Liver Cleanse — through 3 ingredients. Tap an ingredient for the detail:
Turmeric Rhizome, Root ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Rhizome, Root Extract + Abiraterone interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Abiraterone interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with Complete Liver Cleanse — through 3 ingredients. Tap an ingredient for the detail:
Turmeric Rhizome, Root ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Rhizome, Root Extract + Abiraterone Acetate interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Abiraterone Acetate interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with Complete Liver Cleanse — through 7 ingredients. Tap an ingredient for the detail:
NiacinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Niacin + Abrocitinib interactionSeleniumAnticoagulant/antiplatelet Drugs, Immunosuppressants Moderate
Interaction Summary
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Selenium + Abrocitinib interactionN-acetyl L-cysteineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, N-acetyl cysteine might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full N-acetyl L-cysteine + Abrocitinib interactionArtichoke Leaf ExtractCytochrome P450 2c19 (cyp2c19) Substrates Moderate
Interaction Summary
Theoretically, artichoke might increase serum levels of drugs metabolized by CYP2C19.
Read the full Artichoke Leaf Extract + Abrocitinib interactionDandelion Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
Read the full Dandelion Root Extract + Abrocitinib interactionTurmeric Rhizome, Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Rhizome, Root Extract + Abrocitinib interactionMilk Thistle Seed ExtractCytochrome P450 2c9 (cyp2c9) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP2C9; research is conflicting.
Read the full Milk Thistle Seed Extract + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with Complete Liver Cleanse — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Rhizome, Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Rhizome, Root Extract + Acalabrutinib interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Complete Liver Cleanse — through 5 ingredients. Tap an ingredient for the detail:
Milk Thistle Seed ExtractAntidiabetes Drugs Moderate
Interaction Summary
Taking milk thistle with antidiabetes drugs may increase the risk of hypoglycemia.
Read the full Milk Thistle Seed Extract + Acarbose interactionTurmeric Rhizome, Root ExtractHepatotoxic Drugs, Antidiabetes Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Rhizome, Root Extract + Acarbose interactionNiacinAntidiabetes Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Niacin can increase blood glucose levels and may diminish the effects of antidiabetes drugs.
Read the full Niacin + Acarbose interactionDandelion Root ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase the risk for hypoglycemia when used with antidiabetes drugs.
Read the full Dandelion Root Extract + Acarbose interactionArtichoke Leaf ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, artichoke leaf extract may increase the risk of hypoglycemia when taken with antidiabetes drugs.
Read the full Artichoke Leaf Extract + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Complete Liver Cleanse — through 6 ingredients. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs, Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acebutolol interactionArtichoke Leaf ExtractAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, artichoke leaf extract may increase the risk of hypotension when taken with antihypertensive drugs.
Read the full Artichoke Leaf Extract + Acebutolol interactionTurmeric Rhizome, Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Rhizome, Root Extract + Acebutolol interactionTaurineAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taurine might increase the risk of hypotension when taken with antihypertensive drugs.
Read the full Taurine + Acebutolol interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Acebutolol interactionN-acetyl L-cysteineAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, N-acetyl cysteine might increase the risk of hypotension when taken with antihypertensive drugs.
Read the full N-acetyl L-cysteine + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Complete Liver Cleanse — through 5 ingredients. Tap an ingredient for the detail:
N-acetyl L-cysteineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, N-acetyl cysteine might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full N-acetyl L-cysteine + Acenocoumarol interactionNiacinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Niacin + Acenocoumarol interactionSeleniumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Selenium + Acenocoumarol interactionDandelion Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
Read the full Dandelion Root Extract + Acenocoumarol interactionTurmeric Rhizome, Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Rhizome, Root Extract + Acenocoumarol interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with Complete Liver Cleanse — through 5 ingredients. Tap an ingredient for the detail:
Dandelion Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion Root Extract + Acetaminophen interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen interactionTurmeric Rhizome, Root ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Rhizome, Root Extract + Acetaminophen interactionMilk Thistle Seed ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with Complete Liver Cleanse — through 7 ingredients. Tap an ingredient for the detail:
Milk Thistle Seed ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Aspirin interactionTurmeric Rhizome, Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Rhizome, Root Extract + Acetaminophen, Aspirin interactionNiacinHepatotoxic Drugs, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Aspirin interactionDandelion Root ExtractGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Acetaminophen, Aspirin interactionN-acetyl L-cysteineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, N-acetyl cysteine might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full N-acetyl L-cysteine + Acetaminophen, Aspirin interactionSeleniumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Selenium + Acetaminophen, Aspirin interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with Complete Liver Cleanse — through 7 ingredients. Tap an ingredient for the detail:
NiacinAspirin, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Large doses of aspirin might alter the clearance of niacin.
Read the full Niacin + Acetaminophen, Aspirin, Caffeine interactionN-acetyl L-cysteineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, N-acetyl cysteine might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full N-acetyl L-cysteine + Acetaminophen, Aspirin, Caffeine interactionSeleniumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Selenium + Acetaminophen, Aspirin, Caffeine interactionDandelion Root ExtractAnticoagulant/antiplatelet Drugs, Glucuronidated Drugs +1 Moderate
Interaction Summary
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
Read the full Dandelion Root Extract + Acetaminophen, Aspirin, Caffeine interactionTurmeric Rhizome, Root ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +2 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Rhizome, Root Extract + Acetaminophen, Aspirin, Caffeine interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Acetaminophen, Aspirin, Caffeine interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with Complete Liver Cleanse — through 5 ingredients. Tap an ingredient for the detail:
Dandelion Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Read the full Dandelion Root Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionTurmeric Rhizome, Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Rhizome, Root Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionMilk Thistle Seed ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, ButalbitalAxocet, Bancap, Bucet, Butex Forte, Esgic CF, Orbivan CF +5 more
How Acetaminophen, Butalbital interacts with Complete Liver Cleanse — through 6 ingredients. Tap an ingredient for the detail:
Turmeric Rhizome, Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Rhizome, Root Extract + Acetaminophen, Butalbital interactionMilk Thistle Seed ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Butalbital interactionDandelion Root ExtractGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Acetaminophen, Butalbital interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital interactionSeleniumBarbiturates Moderate
Interaction Summary
Theoretically, selenium might prolong the sedating effects of barbiturates.
Read the full Selenium + Acetaminophen, Butalbital interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with Complete Liver Cleanse — through 6 ingredients. Tap an ingredient for the detail:
SeleniumBarbiturates Moderate
Interaction Summary
Theoretically, selenium might prolong the sedating effects of barbiturates.
Read the full Selenium + Acetaminophen, Butalbital, Caffeine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital, Caffeine interactionDandelion Root ExtractGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Acetaminophen, Butalbital, Caffeine interactionTurmeric Rhizome, Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Rhizome, Root Extract + Acetaminophen, Butalbital, Caffeine interactionMilk Thistle Seed ExtractGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Butalbital, Caffeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with Complete Liver Cleanse — through 6 ingredients. Tap an ingredient for the detail:
Turmeric Rhizome, Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Rhizome, Root Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionDandelion Root ExtractGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital, Caffeine, Codeine interactionSeleniumBarbiturates Moderate
Interaction Summary
Theoretically, selenium might prolong the sedating effects of barbiturates.
Read the full Selenium + Acetaminophen, Butalbital, Caffeine, Codeine interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with Complete Liver Cleanse — through 5 ingredients. Tap an ingredient for the detail:
Turmeric Rhizome, Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Rhizome, Root Extract + Acetaminophen, Butalbital, Codeine interactionMilk Thistle Seed ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Butalbital, Codeine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital, Codeine interactionDandelion Root ExtractGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Acetaminophen, Butalbital, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with Complete Liver Cleanse — through 5 ingredients. Tap an ingredient for the detail:
Dandelion Root ExtractGlucuronidated Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
Read the full Dandelion Root Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital, Codeine Phosphate interactionTurmeric Rhizome, Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Rhizome, Root Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionMilk Thistle Seed ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine Phosphate interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Complete Liver Cleanse with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Turmeric Rhizome, Root Extract
Alkylating Agents
Turmeric has antioxidant effects. Theoretically, this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro research suggests that curcumin, a constituent of turmeric, inhibits mechlorethamine-induced apoptosis of breast cancer cells by up to 70%. Also, animal research shows that curcumin inhibits cyclophosphamide-induced tumor regression. However, some in vitro research shows that curcumin does not affect the apoptosis capacity of etoposide. Also, other laboratory research suggests that curcumin might augment the cytotoxic effects of alkylating agents. Reasons for the discrepancies may relate to the dose of curcumin and the specific chemotherapeutic agent. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effect, if any, turmeric might have on alkylating agents.
Amlodipine (Norvasc)
Taking turmeric with amlodipine may increase levels of amlodipine.
Animal research shows that giving amlodipine 1 mg/kg as a single dose following the use of turmeric extract 200 mg/kg daily for 2 weeks increases the maximum concentration and area under the curve by 53% and 56%, respectively, when compared with amlodipine alone. Additional animal research shows that taking amlodipine 1 mg/kg with a curcumin 2 mg/kg pretreatment for 10 days increases the maximum concentration and area under the curve by about 2-fold when compared with amlodipine alone.
Anticoagulant/Antiplatelet Drugs
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs. However, research is conflicting.
Curcumin, a constituent of turmeric, has demonstrated antiplatelet effects in vitro. Furthermore, two case reports have found that taking turmeric along with warfarin or fluindione was associated with an increased international normalized ratio (INR). However, one clinical study in healthy volunteers shows that taking curcumin 500 mg daily for 3 weeks, alone or with aspirin 100 mg, does not increase antiplatelet effects or bleeding risk. It is possible that the dose of turmeric used in this study was too low to produce a notable effect.
Antidiabetes Drugs
Theoretically, taking turmeric with antidiabetes drugs might increase the risk of hypoglycemia.
Animal research and case reports suggest that curcumin, a turmeric constituent, can reduce blood glucose levels in patients with diabetes. Furthermore, clinical research in adults with type 2 diabetes shows that taking curcumin 475 mg daily for 10 days prior to taking glyburide 5 mg decreased postprandial glucose levels for up to 24 hours when compared with glyburide alone, despite the lack of a significant pharmacokinetic interaction. Other clinical studies in patients with diabetes show that taking curcumin daily can reduce blood glucose levels when compared with placebo.
Antitumor Antibiotics
Turmeric has antioxidant effects. Theoretically, this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro and animal research shows that curcumin, a constituent of turmeric, inhibits doxorubicin-induced apoptosis of breast cancer cells by up to 65%. However, curcumin does not seem to affect the apoptosis capacity of daunorubicin. In fact, some research shows that curcumin might augment the cytotoxic effects of antitumor antibiotics, increasing their effectiveness. Reasons for the discrepancies may relate to the dose of curcumin and the chemotherapeutic agent. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effects, if any, antioxidants such as turmeric have on antitumor antibiotics.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
In vitro and animal research show that turmeric and its constituents curcumin and curcuminoids inhibit CYP3A4. Also, 8 case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking turmeric and cancer medications that are CYP3A4 substrates, including everolimus, ruxolitinib, ibrutinib, and palbociclib, and bortezomib. In another case report, a transplant patient presented with acute nephrotoxicity and elevated tacrolimus levels after consuming turmeric powder at a dose of 15 or more spoonfuls daily for ten days prior. It was thought that turmeric increased levels of tacrolimus due to CYP3A4 inhibition.
Conversely, other in vitro research suggests that turmeric induces CYP3A4 activity, leading to reduced levels of CYP3A4 substrates. An animal model suggests that induction of CYP3A4 occurs after daily curcumin use for 1 week. However, the induction of CYP3A4 by turmeric has not been reported in humans.
Hepatotoxic Drugs
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
There is concern that turmeric might cause hepatotoxicity, especially when highly bioavailable formulations are used in high doses.
Methotrexate (Trexall, Others)
Theoretically, turmeric might have additive effects when used with hepatotoxic drugs such as methotrexate.
In one case report, a 39-year-old female taking methotrexate, turmeric, and linseed oil developed hepatotoxicity.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Theoretically, turmeric might increase blood levels of OATP4C1 substrates.
In vitro research shows that the turmeric constituent curcumin competitively inhibits OATP4C1 transport. This transporter is expressed in the kidney and facilitates the renal excretion of certain drugs. Theoretically, taking turmeric might decrease renal excretion of OATP substrates.
Sulfasalazine (Azulfidine)
Turmeric might increase the effects and adverse effects of sulfasalazine.
Clinical research shows that taking the turmeric constituent, curcumin, can increase blood levels of sulfasalazine by 3.2-fold.
Tacrolimus (Prograf)
Turmeric might increase the effects and adverse effects of tacrolimus.
In one case report, a transplant patient presented with acute nephrotoxicity and elevated tacrolimus levels of 29 ng/mL. The patient previously had tacrolimus levels within the therapeutic range at 9.7 ng/mL. Ten days prior to presenting at the emergency room the patient started consumption of turmeric powder at a dose of 15 or more spoonfuls daily. It was thought that turmeric increased levels of tacrolimus due to cytochrome P450 3A4 (CYP3A4) inhibition. In vitro and animal research show that turmeric and its constituent curcumin inhibit CYP3A4.
Talinolol
Turmeric may reduce the absorption of talinolol in some situations.
Clinical research shows that taking curcumin for 6 days decreases the bioavailability of talinolol when taken together on the seventh day. The clinical significance of this effect is unclear.
Tamoxifen (Nolvadex)
Theoretically, turmeric might reduce the levels and clinical effects of tamoxifen.
In a small clinical trial in patients with breast cancer taking tamoxifen 20-30 mg daily, adding curcumin 1200 mg plus piperine 10 mg three times daily reduces the 24-hour area under the curve of tamoxifen and the active metabolite endoxifen by 12.8% and 12.4%, respectively, as well as the maximum concentrations of tamoxifen, when compared with tamoxifen alone. However, in the absence of piperine, the area under the curve for endoxifen and the maximum concentration of tamoxifen were not significantly reduced. Effects were most pronounced in patients who were extensive cytochrome P450 (CYP) 2D6 metabolizers.
Topoisomerase I Inhibitors
Turmeric has antioxidant effects. There is some concern that this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro research shows that curcumin, a constituent of turmeric, inhibits camptothecin-induced apoptosis of breast cancer cells by up to 71%. However, other in vitro research shows that curcumin augments the cytotoxic effects of camptothecin. Reasons for the discrepancies may relate to the dose of curcumin and the chemotherapeutic agents. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effect, if any, turmeric might have.
Tramadol (Ultram)
Theoretically, turmeric might increase or decrease levels of tramadol.
Animal research suggests that a single dose of curcumin, a constituent of turmeric, may increase tramadol's maximum concentration (Cmax) by inhibiting metabolism, while continued daily use for 7 days may reduce the area under the curve (AUC) due to the induction of drug-metabolizing enzymes such as cytochrome P450 3A4 (CYP3A4). However, this interaction has not been reported in humans.
Warfarin (Coumadin)
Turmeric might increase the risk of bleeding with warfarin.
One case of increased international normalized ratio (INR) has been reported for a patient taking warfarin who began taking turmeric. Prior to taking turmeric, the patient had stable INR measurements. Within a few weeks of starting turmeric supplementation, the patient's INR increased to 10. Additionally, curcumin, the active constituent in turmeric, has demonstrated antiplatelet effects in vitro, which may produce additive effects when taken with warfarin.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2. However, research is conflicting.
In vitro and animal research show that the turmeric constituent, curcumin, inhibits CYP1A2. However, other in vitro research suggests that curcumin does not significantly affect CYP1A2.
Docetaxel (Taxotere)
Theoretically, turmeric might increase blood levels of oral docetaxel.
Animal research suggests that the turmeric constituent, curcumin, enhances the oral bioavailability of docetaxel. However, the significance of this interaction is unclear, as this drug is typically administered intravenously in clinical settings.
Estrogens
Theoretically, large amounts of turmeric might interfere with hormone replacement therapy through competition for estrogen receptors.
In vitro research shows that curcumin, a constituent of turmeric, displaces the binding of estrogen to its receptors.
Glyburide (Diabeta, Others)
Theoretically, taking turmeric and glyburide in combination might increase the risk of hypoglycemia.
Clinical research shows that taking curcumin 475 mg daily for 10 days prior to taking glyburide 5 mg increases blood levels of glyburide by 12% at 2 hours after the dose in patients with type 2 diabetes. While maximal blood concentrations of glyburide were not affected, turmeric modestly decreased postprandial glucose levels for up to 24 hours when compared to glyburide alone, possibly due to the hypoglycemic effect of turmeric demonstrated in animal research.
Losartan (Cozaar)
Theoretically, turmeric might increase the effects of losartan.
Research in hypertensive rats shows that taking turmeric can increase the hypotensive effects of losartan.
Norfloxacin (Noroxin)
Theoretically, turmeric might increase the effects and adverse effects of norfloxacin.
Animal research shows that taking curcumin, a turmeric constituent, can increase blood levels of orally administered norfloxacin.
P-Glycoprotein Substrates
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
In vitro and animal research shows that curcuminoids and other constituents found in turmeric can inhibit P-glycoprotein expression and activity.
Paclitaxel (Abraxane, Onxol)
Theoretically, turmeric might alter blood levels of paclitaxel, although any effect may not be clinically relevant.
Clinical research in adults with breast cancer receiving intravenous paclitaxel suggests that taking turmeric may modestly alter paclitaxel pharmacokinetics. Patients received paclitaxel on day 1, followed by either no treatment or turmeric 2 grams daily from days 2-22. Pharmacokinetic modeling suggests that turmeric reduces the maximum concentration and area under the curve of paclitaxel by 12.1% and 7.7%, respectively. However, these changes are not likely to be considered clinically relevant. Conversely, animal research suggests that curcumin, a constituent of turmeric, enhances the oral bioavailability of paclitaxel. However, the significance of this interaction is unclear, as this drug is typically administered intravenously in clinical settings.
Milk Thistle seed extract
Antidiabetes Drugs
Taking milk thistle with antidiabetes drugs may increase the risk of hypoglycemia.
Clinical research shows that milk thistle extract, alone or along with tree turmeric extract, can lower blood glucose levels and glycated hemoglobin (HbA1c) in patients with type 2 diabetes, including those already taking antidiabetes drugs. Additionally, animal research shows that milk thistle extract increases the metformin maximum plasma concentration and area under the curve and decreases the renal clearance of metformin, due to inhibition of the multi-drug and toxin extrusion protein 1 (MATE1) renal tubular transport protein.
Cytochrome P450 2B6 (Cyp2B6) Substrates
Theoretically, milk thistle might inhibit CYP2B6.
An in vitro study shows that silybin, a constituent of milk thistle, binds to and noncompetitively inhibits CYP2B6. Additionally, silybin might downregulate the expression of CYP2B6 by decreasing mRNA and protein levels.
Glucuronidated Drugs
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Laboratory research shows that milk thistle constituents inhibit uridine diphosphoglucuronosyl transferase (UGT), the major phase 2 enzyme that is responsible for glucuronidation. Theoretically, this could decrease the clearance and increase levels of glucuronidated drugs. Other laboratory research suggests that a milk thistle extract of silymarin might inhibit beta-glucuronidase, although the significance of this effect is unclear.
Ledipasvir
Theoretically, milk thistle might increase the levels and clinical effects of ledipasvir.
Animal research in rats shows that milk thistle increases the area under the curve (AUC) for ledipasvir and slows its elimination.
Morphine
Theoretically, concomitant use of milk thistle with morphine might affect serum levels of morphine and either increase or decrease its effects.
Animal research shows that milk thistle reduces serum levels of morphine by up to 66%. In contrast, laboratory research shows that milk thistle constituents inhibit uridine diphosphoglucuronosyl transferase (UGT), the major phase 2 enzyme that is responsible for glucuronidation. Theoretically, this could decrease the clearance and increase morphine levels. The effect of taking milk thistle on morphine metabolism in humans is not known.
Raloxifene (Evista)
Theoretically, milk thistle might decrease the clearance and increase levels of raloxifene.
Laboratory research suggests that the milk thistle constituents silibinin and silymarin inhibit the glucuronidation of raloxifene in the intestines.
Sirolimus (Rapamune)
Milk thistle might decrease the clearance of sirolimus.
Pharmacokinetic research shows that a milk thistle extract of silymarin decreases the apparent clearance of sirolimus in hepatically impaired renal transplant patients. It is unclear if this interaction occurs in patients without hepatic impairment.
Sofosbuvir (Solvaldi)
Theoretically, milk thistle might decrease the levels and clinical effects of sofosbuvir.
Animal research in rats shows that milk thistle reduces the metabolism of sofosbuvir, as well as the hepatic uptake of its active metabolite.
Tamoxifen (Nolvadex)
Theoretically, the milk thistle constituent silibinin might increase tamoxifen levels and interfere with its conversion to an active metabolite.
Animal research suggests that the milk thistle constituent silibinin might increase plasma levels of tamoxifen and alter its conversion to an active metabolite. The mechanism appears to involve inhibition of pre-systemic metabolism of tamoxifen by cytochrome P450 (CYP) 2C9 and CYP3A4, and inhibition of P-glycoprotein-mediated efflux of tamoxifen into the intestine for excretion. Whether this interaction occurs in humans is not known.
Warfarin (Coumadin)
Theoretically, milk thistle might increase the effects of warfarin.
In one case report, a man stabilized on warfarin experienced an increase in INR from 2.64 to 4.12 after taking a combination product containing milk thistle 200 mg daily, as well as dandelion, wild yam, niacinamide, and vitamin B12. Levels returned to normal after stopping the supplement. Although a direct correlation between milk thistle and the change in INR cannot be confirmed, some in vitro research suggests that milk thistle might inhibit cytochrome P450 2C9 (CYP2C9), an enzyme involved in the metabolism of various drugs, including warfarin.
Cytochrome P450 2C9 (Cyp2C9) Substrates
It is unclear if milk thistle inhibits CYP2C9; research is conflicting.
In vitro research suggests that milk thistle might inhibit CYP2C9. Additionally, 3 case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking milk thistle and cancer medications that are CYP2C9 substrates, including imatinib and capecitabine. However, contradictory clinical research shows that milk thistle extract does not inhibit CYP2C9 or significantly affect levels of the CYP2C9 substrate tolbutamide. Differences in results could be due to differences in dosages or formulations utilized.
Cytochrome P450 3A4 (Cyp3A4) Substrates
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
While laboratory research shows conflicting results, pharmacokinetic research shows that taking milk thistle extract 420-1350 mg daily does not significantly affect the metabolism of the CYP3A4 substrates irinotecan, midazolam, or indinavir. However, 8 case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking milk thistle and cancer medications that are CYP3A4 substrates, including gefitinib, sorafenib, doxorubicin, and vincristine.
Estrogens
Theoretically, milk thistle might interfere with estrogen therapy through competition for estrogen receptors.
Animal research suggests that a milk thistle extract of silymarin binds to estrogen receptor beta.
Hmg-Coa Reductase Inhibitors ("Statins")
Theoretically, milk thistle might interfere with statin therapy by decreasing the activity of organic anion transporting polypeptide 1B1 (OATB1B1) and inhibiting breast cancer resistance protein (BCRP).
Preliminary evidence suggests that a milk thistle extract of silymarin can decrease the activity of the OATP1B1, which transports HMG-CoA reductase inhibitors into the liver to their site of action, and animal research shows this increases the maximum plasma concentration of pitavastatin and pravastatin. The silibinin component also inhibits BCRP, which transports statins from the liver into the bile for excretion. However, in a preliminary study in healthy males, silymarin 140 mg three times daily had no effect on the pharmacokinetics of a single 10 mg dose of rosuvastatin.
Indinavir (Crixivan)
Theoretically, milk thistle may induce cytochrome P450 3A4 (CYP3A4) enzymes and increase the metabolism of indinavir; however, results are conflicting.
One pharmacokinetic study shows that taking milk thistle (Standardized Milk Thistle, General Nutrition Corp.) 175 mg three times daily in combination with multiple doses of indinavir 800 mg every 8 hours decreases the mean trough levels of indinavir by 25%. However, results from the same pharmacokinetic study show that milk thistle does not affect the overall exposure to indinavir. Furthermore, two other pharmacokinetic studies show that taking specific milk thistle extract (Legalon, Rottapharm Madaus; Thisilyn, Nature's Way) 160-450 mg every 8 hours in combination with multiple doses of indinavir 800 mg every 8 hours does not reduce levels of indinavir.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Milk thistle may inhibit one form of OATP, OATP-B1, which could reduce the bioavailability and clinical effects of OATP-B1 substrates.
In vitro research shows that milk thistle inhibits OATP-B1. Two case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking milk thistle and cancer medications that are OATP substrates, including sorafenib and methotrexate. OATPs are expressed in the small intestine and liver and are responsible for the uptake of drugs and other compounds into the body. Inhibition of OATP may reduce the bioavailability of oral drugs that are substrates of OATP.
P-Glycoprotein Substrates
Theoretically, milk thistle might increase the absorption of P-glycoprotein substrates. However, this effect does not seem to be clinically significant.
In vitro research shows that milk thistle can inhibit P-glycoprotein activity and 1 case report from the World Health Organization (WHO) adverse drug reaction database describes increased abdominal pain in a patient taking milk thistle and the cancer medication vincristine, a P-glycoprotein substrate, though this patient was also taking methotrexate. However, a small pharmacokinetic study in healthy volunteers shows that taking milk thistle (Enzymatic Therapy Inc.) 900 mg, standardized to 80% silymarin, in 3 divided doses daily for 14 days does not affect absorption of digoxin, a P-glycoprotein substrate.
Niacin
Alcohol (Ethanol)
Concomitant use of alcohol and niacin might increase the risk of flushing and hepatotoxicity.
Alcohol can exacerbate the flushing and pruritus associated with niacin. Large doses of niacin might also exacerbate liver dysfunction associated with chronic alcohol use. A case report describes delirium and lactic acidosis in a patient taking niacin 3 grams daily who ingested 1 liter of wine. Advise patients to avoid large amounts of alcohol while taking niacin.
Allopurinol (Zyloprim)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as allopurinol.
Large doses of niacin can reduce urinary excretion of uric acid, potentially resulting in hyperuricemia. Doses of uricosurics such as allopurinol might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Anticoagulant/Antiplatelet Drugs
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Several cases of clotting factor synthesis deficiency and coagulopathy have been reported in patients taking sustained-release niacin. Also, thrombocytopenia has been reported in patients treated with niacin or niacin plus lovastatin.
Antidiabetes Drugs
Niacin can increase blood glucose levels and may diminish the effects of antidiabetes drugs.
Niacin impairs glucose tolerance in a dose-dependent manner, probably by causing or aggravating insulin resistance and increasing hepatic production of glucose. In diabetes patients, niacin 4.5 grams daily for 5 weeks can increase plasma glucose by an average of 16% and glycated hemoglobin (HbA1c) by 21%. However, lower doses of 1.5 grams daily or less appear to have minimal effects on blood glucose. In some patients, glucose levels increase when niacin is started, but then return to baseline when a stable dose is reached. Up to 35% of patients with diabetes may need adjustments in hypoglycemic therapy when niacin is added.
Antihypertensive Drugs
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
The vasodilating effects of niacin can cause hypotension. Furthermore, some clinical evidence suggests that a one-hour infusion of niacin can reduce systolic, diastolic, and mean blood pressure in hypertensive patients. This effect is not observed in normotensive patients.
Bile Acid Sequestrants
Bile acid sequestrants can bind niacin and decrease absorption. Separate administration by 4-6 hours to avoid an interaction.
In vitro studies show that colestipol (Colestid) binds about 98% of available niacin and cholestyramine (Questran) binds 10% to 30%.
Gemfibrozil (Lopid)
Theoretically, concomitant use of niacin and gemfibrozil might increase the risk of myopathy in some patients.
A case of myopathy from concomitant use of niacin and gemfibrozil has been reported. Niacin alone has also been associated with cases of myopathy. Using gemfibrozil with niacin might further increase the risk of developing myopathy.
Hepatotoxic Drugs
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Niacin has been associated with cases of liver toxicity, especially when used in pharmacologic doses. Sustained-release niacin preparations appear to be associated with a higher risk of hepatotoxicity than immediate-release niacin.
Hmg-Coa Reductase Inhibitors ("Statins")
Theoretically, concomitant use of niacin and statins might increase the risk of myopathy and rhabdomyolysis in some patients.
Some case reports have raised concerns that niacin might increase the risk of myopathy and rhabdomyolysis when combined with statins. However, a significantly increased risk of myopathy has not been demonstrated in clinical trials, including those using an FDA-approved combination of lovastatin and niacin (Advicor).
Probenecid (Benemid)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as probenecid.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as probenecid might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Sulfinpyrazone (Anturane)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as sulfinpyrazone.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as sulfinpyrazone might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Thyroid Hormone
Theoretically, niacin might antagonize the therapeutic effects of thyroid hormones.
Clinical research and case reports suggests that taking niacin can reduce serum levels of thyroxine-binding globulin by up to 25% and moderately reduce levels of thyroxine (T4). Patients taking thyroid hormone for hypothyroidism might need dose adjustments when using niacin.
Transdermal Nicotine (Nicoderm)
Theoretically, concomitant use of niacin and transdermal nicotine might increase the risk of flushing and dizziness.
Niacin and nicotine can both cause flushing and dizziness.
Warfarin (Coumadin)
There is limited evidence that niacin may increase the anticoagulant effects of warfarin.
In a case report, a patient on warfarin developed an elevated international normalized ratio (INR) of 3.9 after taking niacin for two weeks. The patient's INR was previously stable, ranging between 2 and 3 in recent months, and no other medication changes were identified. The elevated INR returned to therapeutic range within 4 days following the discontinuation of niacin.
Aspirin
Large doses of aspirin might alter the clearance of niacin.
Aspirin is often used with niacin to reduce niacin-induced flushing. Doses of 80-975 mg aspirin have been used, but 325 mg appears to be optimal. Aspirin also seems to reduce the clearance of niacin by competing for glycine conjugation. Taking aspirin 1 gram seems to reduce niacin clearance by 45%. This is probably a dose-related effect and not clinically significant with the more common aspirin dose of 325 mg.
Dandelion Root Extract
Anticoagulant/Antiplatelet Drugs
Theoretically, taking dandelion root along with anticoagulant or antiplatelet drugs might increase the risk of bruising and bleeding.
In vitro research suggests that dandelion root inhibits platelet aggregation.
Antidiabetes Drugs
Theoretically, dandelion might increase the risk for hypoglycemia when used with antidiabetes drugs.
Laboratory research suggests that dandelion extract may have moderate alpha-glucosidase inhibitor activity and might also increase insulin secretion. Also, in a case report, a 58-year-old woman with type 2 diabetes who was being treated with insulin developed hypoglycemia 2 weeks after beginning to eat salads containing dandelion.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, dandelion might increase levels of drugs metabolized by CYP1A2.
Laboratory research suggests that dandelion might inhibit CYP1A2. So far, this interaction has not been reported in humans. However, until more is known, watch for an increase in the levels of drugs metabolized by CYP1A2 in patients taking dandelion.
Glucuronidated Drugs
Theoretically, dandelion might increase the clearance of drugs that are UDP-glucuronosyltransferase substrates.
There is some preliminary evidence that dandelion might induce UDP-glucuronosyltransferase, a phase II enzyme.
Lithium
Theoretically, through diuretic effects, dandelion might reduce excretion and increase levels of lithium.
Animal research suggests that dandelion has diuretic properties. As diuretics can increase serum lithium levels, the dose of lithium might need to be decreased when taken with dandelion.
Potassium-Sparing Diuretics
Theoretically, dandelion might increase the risk of hyperkalemia when taken with potassium-sparing diuretics.
Dandelion contains significant amounts of potassium.
Quinolone Antibiotics
Theoretically, dandelion might lower fluoroquinolone levels.
Animal research shows that dandelion reduces absorption of ciprofloxacin and can lower levels by 73%. However, this effect has not been reported in humans.
Artichoke leaf extract
Antidiabetes Drugs
Theoretically, artichoke leaf extract may increase the risk of hypoglycemia when taken with antidiabetes drugs.
A meta-analysis of small clinical studies shows that taking artichoke leaf extract for 8-12 weeks can modestly reduce fasting plasma glucose when compared with placebo.
Antihypertensive Drugs
Theoretically, artichoke leaf extract may increase the risk of hypotension when taken with antihypertensive drugs.
A meta-analysis of small clinical studies in patients with hypertension shows that taking artichoke can reduce systolic blood pressure by around 3 mmHg and diastolic blood pressure by around 2 mmHg when compared with placebo.
Cytochrome P450 2B6 (Cyp2B6) Substrates
Theoretically, artichoke might increase serum levels of drugs metabolized by CYP2B6.
In vitro research shows that artichoke leaf extract inhibits CYP2B6 activity. However, this interaction has not been reported in humans.
Cytochrome P450 2C19 (Cyp2C19) Substrates
Theoretically, artichoke might increase serum levels of drugs metabolized by CYP2C19.
In vitro research shows that artichoke leaf extract inhibits CYP2C19 activity. However, this interaction has not been reported in humans.
Selenium
Anticoagulant/Antiplatelet Drugs
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Clinical research suggests that taking selenium 10 mcg/kg/day can increase bleeding times by increasing prostacyclin production, which inhibits platelet activity. Other clinical research suggests that taking selenium 75 mcg daily, in combination with ascorbic acid 600 mg, alpha-tocopherol 300 mg, and beta-carotene 27 mg, reduces platelet aggregation.
Barbiturates
Theoretically, selenium might prolong the sedating effects of barbiturates.
Laboratory research suggests that selenium can inhibit the hepatic metabolism of barbiturates. Selenium seems to prolong the sedative effect of pentobarbital in animal models.
Immunosuppressants
Theoretically, selenium supplementation may reduce the effectiveness of immunosuppressant therapy.
In vitro research and preliminary clinical evidence suggests that selenium may stimulate the immune system.
Warfarin (Coumadin)
Theoretically, selenium might interfere with warfarin activity.
Animal research suggests that selenium can increase warfarin activity. Selenium might interact with warfarin by displacing it from albumin binding sites, reducing its metabolism in the liver, or by decreasing production of vitamin K-dependent clotting factors. Selenium can also prolong bleeding times in humans by increasing prostacyclin production, which inhibits platelet activity.
Contraceptive Drugs
Contraceptive drugs might increase levels of selenium, although the clinical significance of this effect is unclear.
Some research suggests that oral contraceptives increase serum selenium levels in women taking oral contraceptives; however, other research shows no change in selenium levels. It is suggested that an increase could be due to increased carrier proteins, indicating a redistribution of selenium rather than a change in total body selenium.
Niacin
Selenium might reduce the beneficial effects of niacin on high-density lipoprotein (HDL) levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as selenium, or to the combination. It also is not known whether it will occur in other patient populations.
N-Acetyl L-Cysteine
Nitroglycerin
N-acetyl cysteine can increase the risk for hypotension and headaches when taken with intravenous or transdermal nitroglycerin.
Clinical research shows that concomitant administration of N-acetyl cysteine and intravenous or transdermal nitroglycerin can cause severe hypotension and intolerable headaches. Furthermore, in vitro research suggests that N-acetyl cysteine increases the anticoagulant activity of nitroglycerin.
Activated Charcoal
N-acetyl cysteine might reduce the effects of activated charcoal, while activated charcoal might reduce the absorption of N-acetyl cysteine.
N-acetyl cysteine appears to reduce the capacity of activated charcoal to adsorb acetaminophen and salicylic acid. Conversely, although clinical research suggests that although activated charcoal can reduce the absorption of N-acetyl cysteine by up to 40%, it does not seem to reduce its clinical effects. Other clinical evidence suggests that activated charcoal does not affect the absorption of N-acetyl cysteine.
Anticoagulant/Antiplatelet Drugs
Theoretically, N-acetyl cysteine might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Clinical research suggests that intravenous N-acetyl cysteine decreases prothrombin time, prolongs coagulation time, decreases platelet aggregation, and increases blood loss in surgical patients. Furthermore, in vitro research suggests that N-acetyl cysteine increases the anticoagulant activity of nitroglycerin.
Antihypertensive Drugs
Theoretically, N-acetyl cysteine might increase the risk of hypotension when taken with antihypertensive drugs.
Animal research suggests that N-acetyl cysteine potentiates the hypotensive effects of the angiotensin-converting enzyme inhibitors (ACEIs) captopril and enalaprilat. Theoretically, combining N-acetyl cysteine with other antihypertensive drugs might increase the risk of hypotension.
Chloroquine (Aralen)
Theoretically, N-acetyl cysteine might interfere with the antimalarial effects of chloroquine.
Animal research suggests that N-acetyl cysteine might reduce the antimalarial effects of chloroquine by increasing cellular levels of glutathione.
Vitamin B6
Amiodarone (Cordarone)
Theoretically, vitamin B6 might increase the photosensitivity caused by amiodarone.
Despite initial case reports suggesting that pyridoxine may have a protective effect against amiodarone-induced photosensitivity, preliminary clinical research suggests that pyridoxine may actually exacerbate this adverse effect.
Antihypertensive Drugs
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Research in hypertensive rats shows that vitamin B6 can decrease systolic blood pressure. Similarly, clinical research in patients with hypertension shows that taking high doses of vitamin B6 may reduce systolic and diastolic blood pressure, possibly by reducing plasma levels of epinephrine and norepinephrine.
Phenobarbital (Luminal)
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenobarbital, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenobarbital to avoid high doses of vitamin B6.
Phenytoin (Dilantin)
High doses of vitamin B6 may reduce the levels and clinical effects of phenytoin.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenytoin, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenytoin to avoid high doses of vitamin B6.
Levodopa
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Vitamin B6 (pyridoxine) enhances the metabolism of levodopa, reducing its clinical effects. However, this interaction does not occur when carbidopa is used concurrently with levodopa (Sinemet). Therefore, it is not likely to be a problem in most people.
Vitamin C
Alkylating Agents
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin C have on chemotherapy.
Aluminum
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Research in animals and humans shows that vitamin C increases aluminum absorption, theoretically by chelating aluminum and keeping it in solution where it is available for absorption. In people with normal renal function, urinary excretion of aluminum will likely increase, making aluminum retention and toxicity unlikely. Patients with renal failure who take aluminum-containing compounds such as phosphate binders should avoid vitamin C supplements in doses above the recommended dietary allowances.
Antitumor Antibiotics
Theoretically, the antioxidant effects of vitamin C might reduce the effectiveness of antitumor antibiotics.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as doxorubicin. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effects, if any, antioxidants such as vitamin C have on chemotherapy.
Estrogens
Vitamin C might increase blood levels of estrogens.
Increases in plasma estrogen levels of up to 55% occur under some circumstances when vitamin C is taken concurrently with oral contraceptives or hormone replacement therapy, including topical products. It is suggested that vitamin C prevents oxidation of estrogen in the tissues, regenerates oxidized estrogen, and reduces sulfate conjugation of estrogen in the gut wall. When tissue levels of vitamin C are high, these processes are already maximized and supplemental vitamin C does not have any effect on estrogen levels. Increases in plasma estrogen levels may occur when patients who are deficient in vitamin C take supplements. Monitor these patients for estrogen-related side effects.
Fluphenazine (Prolixin)
Theoretically, vitamin C might decrease levels of fluphenazine.
In one patient there was a clinically significant decrease in fluphenazine levels when vitamin C (500 mg twice daily) was started. The mechanism is not known, and there is no further data to confirm this interaction.
Indinavir (Crixivan)
Vitamin C can modestly reduce indinavir levels.
One pharmacokinetic study shows that taking vitamin C 1 gram orally once daily along with indinavir 800 mg orally three times daily reduces the area under the concentration-time curve of indinavir by 14%. The mechanism of this interaction is unknown, but it is unlikely to be clinically significant in most patients. The effect of higher doses of vitamin C on indinavir levels is unknown.
Levothyroxine (Synthroid, Others)
Vitamin C can increase levothyroxine absorption.
Two clinical studies in adults with poorly controlled hypothyroidism show that swallowing levothyroxine with a glass of water containing vitamin C 500-1000 mg in solution reduces thyroid stimulating hormone (TSH) levels and increases thyroxine (T4) levels when compared with taking levothyroxine alone. This suggests that vitamin C increases the oral absorption of levothyroxine, possibly due to a reduction in pH.
Warfarin (Coumadin)
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Vitamin C in high doses may cause diarrhea and possibly reduce warfarin absorption. There are reports of two people who took up to 16 grams daily of vitamin C and had a reduction in prothrombin time. Lower doses of 5-10 grams daily can also reduce warfarin absorption. In many cases, this does not seem to be clinically significant. However, a case of warfarin resistance has been reported for a patient who took vitamin C 500 mg twice daily. Cessation of vitamin C supplementation resulted in a rapid increase in international normalized ratio (INR). Tell patients taking warfarin to avoid taking vitamin C in excessively high doses (greater than 10 grams daily). Lower doses may be safe, but the anticoagulation activity of warfarin should be monitored. Patients who are stabilized on warfarin while taking vitamin C should avoid adjusting vitamin C dosage to prevent the possibility of warfarin resistance.
Acetaminophen (Tylenol, Others)
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
A small pharmacokinetic study in healthy volunteers shows that taking high-dose vitamin C (3 grams) 1.5 hours after taking acetaminophen 1 gram slightly increases the apparent half-life of acetaminophen from around 2.3 hours to 3.1 hours. Ascorbic acid competitively inhibits sulfate conjugation of acetaminophen. However, to compensate, elimination of acetaminophen glucuronide and unconjugated acetaminophen increases. This effect is not likely to be clinically significant.
Aspirin
Acidification of the urine by vitamin C might increase aspirin levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction is not clinically significant.
Choline Magnesium Trisalicylate (Trilisate)
Acidification of the urine by vitamin C might increase choline magnesium trisalicylate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Niacin
Vitamin C might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as vitamin C, or to the combination. It also is not known whether it will occur in other patient populations.
Salsalate (Disalcid)
Acidification of the urine by vitamin C might increase salsalate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams/day vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Taurine
Antihypertensive Drugs
Theoretically, taurine might increase the risk of hypotension when taken with antihypertensive drugs.
Some clinical evidence suggests that taurine can reduce both systolic and diastolic blood pressure.
Lithium
Theoretically, taurine might reduce excretion and increase plasma levels of lithium.
Taurine is thought to have diuretic properties, which might reduce the excretion of lithium.
Calcium D-Glucarate
Ceftriaxone (Rocephin)
Co-administration of intravenous calcium and ceftriaxone can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys.
Avoid administering intravenous calcium in any form, such as parenteral nutrition or Lactated Ringers, within 48 hours of intravenous ceftriaxone. Case reports in neonates show that administering intravenous ceftriaxone and calcium can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys. In several cases, neonates have died as a result of this interaction. So far there are no reports in adults; however, there is still concern that this interaction might occur in adults.
Dolutegravir (Tivicay)
Calcium seems to reduce levels of dolutegravir.
Advise patients to take dolutegravir either 2 hours before or 6 hours after taking calcium supplements. Pharmacokinetic research suggests that taking calcium carbonate 1200 mg concomitantly with dolutegravir 50 mg reduces plasma levels of dolutegravir by almost 40%. Calcium appears to decrease levels of dolutegravir through chelation.
Elvitegravir (Vitekta)
Calcium seems to reduce levels of elvitegravir.
Advise patients to take elvitegravir either 2 hours before or 2 hours after taking calcium supplements. Pharmacokinetic research suggests that taking calcium along with elvitegravir can reduce blood levels of elvitegravir through chelation.
Aluminum
Calcium citrate might increase aluminum absorption and toxicity. Other types of calcium do not increase aluminum absorption.
Calcium citrate can increase the absorption of aluminum when taken with aluminum hydroxide. The increase in aluminum levels may become toxic, particularly in individuals with kidney disease. However, the effect of calcium citrate on aluminum absorption is due to the citrate anion rather than calcium cation. Calcium acetate does not appear to increase aluminum absorption.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Calcium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide and calcium can be taken together if taken with food. However, if taken on an empty stomach, bictegravir/emtricitabine/tenofovir alafenamide should not be taken with, or 2 hours after, calcium containing products.
Bisphosphonates
Calcium reduces the absorption of bisphosphonates.
Advise patients to take bisphosphonates at least 30 minutes before calcium, but preferably at a different time of day. Calcium supplements decrease absorption of bisphosphonates.
Calcipotriene (Dovonex)
Taking calcipotriene with calcium might increase the risk for hypercalcemia.
Calcipotriene is a vitamin D analog used topically for psoriasis. It can be absorbed in sufficient amounts to cause systemic effects, including hypercalcemia. Theoretically, combining calcipotriene with calcium supplements might increase the risk of hypercalcemia.
Digoxin (Lanoxin)
Using intravenous calcium with digoxin might increase the risk of fatal cardiac arrhythmias.
Hypercalcemia increases the risk of fatal cardiac arrhythmias with digoxin. However, one retrospective analysis of clinical data suggests that intravenous calcium does not increase the risk of dysrhythmias or mortality in patients receiving digoxin.
Diltiazem (Cardizem, Others)
Theoretically, calcium may reduce the therapeutic effects of diltiazem.
Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically, calcium might increase this risk of hypercalcemia and reduce the effectiveness of diltiazem.
Levothyroxine (Synthroid, Others)
Calcium seems to reduce the absorption and effectiveness of levothyroxine.
Advise patients to take levothyroxine and calcium supplements at least 4 hours apart. Calcium reduces levothyroxine absorption, probably by forming insoluble complexes. Calcium carbonate supplements reduce effectiveness of levothyroxine in patients with hypothyroidism.
Lithium
Theoretically, concomitant use of calcium and lithium may increase this risk of hypercalcemia.
Clinical research suggests that long-term use of lithium may cause hypercalcemia in 10% to 60% of patients. Theoretically, concomitant use of lithium and calcium supplements may further increase this risk.
Quinolone Antibiotics
Calcium seems to reduce the absorption of quinolone antibiotics.
Advise patients to take oral quinolones at least 2 hours before or 4-6 hours after calcium supplements or calcium-fortified foods. Taking calcium at the same time as oral quinolones can reduce quinolone absorption. Calcium binds to quinolones in the gut.
Raltegravir (Isentress)
Calcium may reduce levels of raltegravir.
Pharmacokinetic research shows that taking a single dose of calcium carbonate 3000 mg along with raltegravir 400 mg twice daily modestly decreases the mean area under the curve of raltegravir, but the decrease does not necessitate a dose adjustment of raltegravir. However, a case of elevated HIV-1 RNA levels and documented resistance to raltegravir has been reported for a patient taking calcium carbonate 1 gram three times daily plus vitamin D3 (cholecalciferol) 400 IU three times daily in combination with raltegravir 400 mg twice daily for 11 months. It is thought that calcium reduced raltegravir levels by chelation, leading to treatment failure.
Sotalol (Betapace)
Calcium seems to reduce the absorption of sotalol.
Advise patients to separate doses by at least 2 hours before or 4-6 hours after calcium. Calcium appears to reduce the absorption of sotalol, probably by forming insoluble complexes.
Tetracycline Antibiotics
Calcium seems to reduce the absorption of tetracycline antibiotics.
Advise patients to take oral tetracyclines at least 2 hours before, or 4-6 hours after calcium supplements. Taking calcium at the same time as oral tetracyclines can reduce tetracycline absorption. Calcium binds to tetracyclines in the gut.
Thiazide Diuretics
Taking calcium along with thiazides might increase the risk of hypercalcemia and renal failure.
Thiazides reduce calcium excretion by the kidneys. Using thiazides along with moderately large amounts of calcium carbonate increases the risk of milk-alkali syndrome (hypercalcemia, metabolic alkalosis, renal failure). Patients may need to have their serum calcium levels and/or parathyroid function monitored regularly.
Verapamil (Calan, Others)
Theoretically, calcium may reduce the therapeutic effects of verapamil.
Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically, use of calcium supplements may increase this risk of hypercalcemia and reduce the effectiveness of verapamil.
Calcium Channel Blockers
Intravenous calcium may decrease the effects of calcium channel blockers; oral calcium is unlikely to have this effect.
Intravenous calcium is used to decrease the effects of calcium channel blockers in the management of overdose. Intravenous calcium gluconate has been used before intravenous verapamil (Isoptin) to prevent or reduce the hypotensive effects without affecting the antiarrhythmic effects. But there is no evidence that dietary or supplemental calcium when taken orally interacts with calcium channel blockers.
L-Glutamine
Anticonvulsants
Theoretically, glutamine might antagonize the effects of anticonvulsant medications.
Glutamine is metabolized to the excitatory neurotransmitter glutamate. Glutamate might have antagonistic effects with anticonvulsant drugs. However, this interaction has not yet been reported in humans.
Folic Acid
5-Fluorouracil
Theoretically, high doses of folic acid might increase the toxicity of 5-fluorouracil.
Increases in gastrointestinal side effects of 5-fluorouracil, such as stomatitis and diarrhea, have been described in two clinical studies when leucovorin, a form of folic acid, was administered with 5-fluorouracil.
Capecitabine (Xeloda)
Use of high-dose folic acid might contribute to capecitabine toxicity.
Clinical research suggests that higher serum folate levels are associated with an increased risk for moderate or severe toxicity during capecitabine-based treatment for colorectal cancer. Additionally, in one case report, taking folic acid 15 mg daily might have contributed to increased toxicity, including severe diarrhea, vomiting, edema, hand-foot syndrome, and eventually death, in a patient prescribed capecitabine.
Methotrexate (Trexall, Others)
Folic acid might reduce the efficacy of methotrexate as a cancer treatment when given concurrently.
Methotrexate exerts its cytotoxic effects by preventing conversion of folic acid to the active form needed by cells. There is some evidence that folic acid supplements reduce the efficacy of methotrexate in the treatment of acute lymphoblastic leukemia, and theoretically they could reduce its efficacy in the treatment of other cancers. Advise cancer patients to consult their oncologist before using folic acid supplements. In patients treated with long-term, low-dose methotrexate for rheumatoid arthritis (RA) or psoriasis, folic acid supplements can reduce the incidence of side effects, without reducing efficacy.
Phenobarbital (Luminal)
Folic acid might have antagonistic effects on phenobarbital and increase the risk for seizures.
Folic acid can have direct convulsant activity in some people, reversing the effects of phenobarbital and worsening seizure control. Monitor closely for increased seizure activity.
Phenytoin (Dilantin)
Folic acid might reduce serum levels of phenytoin in some patients.
Folic acid may be a cofactor in phenytoin metabolism. Folic acid, in doses of 1 mg daily or more, can reduce serum levels of phenytoin in some patients. Increases in seizure frequency have been reported. If folic acid supplements are added to established phenytoin therapy, monitor serum phenytoin levels closely. If phenytoin and folic acid are started at the same time and continued together, adverse changes in phenytoin pharmacokinetics are avoided. Note that phenytoin also reduces serum folate levels.
Primidone (Mysoline)
Folic acid might have antagonistic effects on primidone and increase the risk for seizures.
Folic acid can have direct convulsant activity in some people, reversing the effects of primidone and worsening seizure control. Monitor closely for increased seizure activity. Note that primidone also reduces serum folate levels.
Pyrimethamine (Daraprim)
Folic acid might antagonize the effects of pyrimethamine.
Folic acid can antagonize the antiparasitic effects of pyrimethamine against toxoplasmosis and Pneumocystis carinii pneumonia. Folic acid doesn't antagonize the effects of pyrimethamine in the treatment of malaria, because malarial parasites cannot use exogenous folic acid. Use folinic acid as an alternative to folic acid when indicated.
Vitamin B12
Metformin (Glucophage)
Metformin, a common medication used to manage type 2 diabetes, has been associated with lower vitamin B12 levels in some individuals. Prolonged use of metformin can interfere with the absorption of B12 in the digestive system, potentially leading to a deficiency in this essential vitamin.
Riboflavin
Tetracycline Antibiotics
Theoretically, taking riboflavin with tetracycline antibiotics may decrease the potency of these antibiotics.
In vitro research suggests that riboflavin may inhibit the potency of tetracycline antibiotics. It is not clear if this effect is clinically significant, as this interaction has not been reported in humans.
Thiamine
Trimethoprim (Proloprim)
Trimethoprim might increase blood levels of thiamine.
In vitro, animal, and clinical research suggest that trimethoprim inhibits intestinal thiamine transporter ThTR-2, hepatic transporter OCT1, and renal transporters OCT2, MATE1, and MATE2, resulting in paradoxically increased thiamine plasma concentrations.
Glycine
Clozapine (Clozaril)
Theoretically, glycine might decrease the effectiveness of clozapine.
One small clinical study in patients with schizophrenia shows that adding glycine to clozapine therapy worsens symptoms of schizophrenia when compared with clozapine alone. The mechanism of this interaction is unclear.
Brand information
Manufacturer and brand details for Complete Liver Cleanse, from the product label.
Nature's Way
See all Nature's Way products- Name
- Nature's Way Brands, LLC
- City
- Green Bay
- State
- WI
- ZipCode
- 54311
- Phone Number
- 1-800-962-8873
- Web Address
- naturesway.com
Complete Liver Cleanse by Nature's Way: Common Questions
Does Complete Liver Cleanse by Nature's Way interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Is this safe to take if I'm pregnant or breastfeeding?
What does N-acetyl cysteine do in this formula?
Can this cleanse my liver?
Does this contain any fillers or binders?
Will this interact with my diabetes or blood pressure medication?
What's the difference between the herbal extracts—milk thistle, dandelion, and artichoke?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Complete Liver Cleanse is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Complete Liver Cleanse’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin B6
Interacts with 210 drugsVitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is best known for helping with pregnancy-rel...
Read the full Vitamin B6 monograph → Herb & supplement monographVitamin B12
Interacts with 20 drugsVitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very helpful for people who are deficient — su...
Read the full Vitamin B12 monograph → Herb & supplement monographRiboflavin
Interacts with 20 drugsRiboflavin (vitamin B2) is an essential nutrient your body needs to turn food into energy and to keep skin, eyes, and nerves healthy. It is generally very safe at typical doses, and the stro...
Read the full Riboflavin monograph → Herb & supplement monographVitamin C
Interacts with 207 drugsVitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for immune function, collagen, and acts as an...
Read the full Vitamin C monograph → Herb & supplement monographNiacin
Interacts with 727 drugsNiacin (vitamin B3) is an essential nutrient your body needs for energy and metabolism, and deficiency is uncommon in most developed countries. Prescription-strength niacin has been used to...
Read the full Niacin monograph → Herb & supplement monographFolic Acid
Interacts with 40 drugsFolic acid is the man-made form of vitamin B9 and is one of the most well-studied supplements, especially for preventing serious birth defects when taken before and during early pregnancy. I...
Read the full Folic Acid monograph → Herb & supplement monographSelenium
Interacts with 321 drugsSelenium is an essential trace mineral your body needs in small amounts for thyroid function, antioxidant defense, and immune health. Most people who eat a varied diet get enough, and supple...
Read the full Selenium monograph → Herb & supplement monographCalcium
Interacts with 168 drugsCalcium is an essential mineral your body needs for strong bones, nerve signaling, and muscle function, and supplements can help fill gaps when diet falls short. Most people do best getting...
Read the full Calcium monograph → Herb & supplement monographMilk Thistle
Interacts with 954 drugsMilk thistle is a popular herbal supplement most often used for liver health, and its main active component is a group of compounds called silymarin. While it is generally well tolerated, th...
Read the full Milk Thistle monograph → Herb & supplement monographArtichoke
Interacts with 363 drugsArtichoke leaf extract is a generally well-tolerated supplement that may have a mild cholesterol-lowering effect and is often used for indigestion, though the evidence is modest. It is not a...
Read the full Artichoke monograph → Herb & supplement monographDandelion
Interacts with 457 drugsDandelion is a common plant used in food and traditional medicine, often promoted as a natural 'water pill' and digestive aid. Human evidence for these uses is very limited, so its benefits...
Read the full Dandelion monograph → Herb & supplement monographThiamine
Interacts with 3 drugsThiamine (vitamin B1) is an essential nutrient your body needs to turn food into energy and to keep your nerves and heart healthy. Most people get enough from food, but supplements are clear...
Read the full Thiamine monograph → Herb & supplement monographGlutathione
Glutathione is a powerful antioxidant your body makes naturally, and many people take it as a supplement hoping for skin, detox, or anti-aging benefits. However, strong human evidence is lim...
Read the full Glutathione monograph → Herb & supplement monographTurmeric
Interacts with 1,133 drugsTurmeric is a popular spice whose main active compounds, curcuminoids, are studied mostly for inflammation and joint pain. Some research is promising, but quality is mixed and curcumin is po...
Read the full Turmeric monograph → Herb & supplement monographGlutamine
Interacts with 50 drugsGlutamine is the most abundant amino acid in the body and is usually made in your muscles. A prescription form is FDA-approved to help reduce sickle cell disease complications, but for most...
Read the full Glutamine monograph → Herb & supplement monographGlycine
Interacts with 1 drugGlycine is a non-essential amino acid your body makes on its own and that also appears in protein-rich foods. It is most studied for improving sleep quality, where early research is promisin...
Read the full Glycine monograph → Herb & supplement monographTaurine
Interacts with 173 drugsTaurine is an amino acid your body makes naturally and that you also get from animal foods. It is widely used in energy drinks and sports supplements, and short-term use appears generally sa...
Read the full Taurine monograph → Herb & supplement monographN-acetyl Cysteine (nac)
Interacts with 294 drugsN-acetyl cysteine (NAC) is a supplement form of the amino acid cysteine and a building block for the antioxidant glutathione. It has well-established prescription uses for acetaminophen over...
Read the full N-acetyl Cysteine (nac) monograph → Herb & supplement monographMethionine
Methionine is an essential amino acid that your body needs for protein building and many basic chemical reactions. Most people get enough from a normal diet, and supplements are generally no...
Read the full Methionine monograph →Sources & How We Checked
Complete Liver Cleanse's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 695 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Glutamine 11 references
- Miller AL. Therapeutic considerations of L-glutamine: a review of the literature. Altern Med Rev 1999;4:239-48..
- Bozzetti F, Biganzoli L, Gavazzi C, et al. Glutamine supplementation in cancer patients receiving chemotherapy: a double-blind randomized study. Nutrition 1997;13:748-51.. PubMed
- Mebane AH. L-Glutamine and mania. Am J Psychiatry 984;141:1302-3.
- Meldrum BS. Glutamate as a neurotransmitter in the brain: review of physiology and pathology. J Nutr 2000;130:1007S-15S.. PubMed
- Garlick PJ. Assessment of the safety of glutamine and other amino acids. J Nutr 2001;131:2556S-61S.. PubMed
- Chapman AG. Glutamate and epilepsy. J Nutr 2000;130:1043S-5S.. PubMed
- Ziegler TR. Glutamine supplementation in cancer patients receiving bone marrow transplantation and high dose chemotherapy. J Nutr 2001;131:2578S-84S.. PubMed
- Laviano A, Molfino A, Lacaria MT, Canelli A, De Leo S, Preziosa I, Rossi Fanelli F. Glutamine supplementation favors weight loss in nondieting obese female patients. A pilot study. Eur J Clin Nutr. 2014 Nov;68(11):1264-6. PubMed
- Endari (l-glutamine) [package insert]. Torrance, CA: Emmaus Medical,Inc; 2017.
- Niihara Y, Miller ST, Kanter J, et al. A Phase 3 Trial of l-Glutamine in Sickle Cell Disease. N Engl J Med 2018;379(3):226-35. doi: 10.1056/NEJMoa1715971.
- Ogden HB, Child RB, Fallowfield JL, et al. Gastrointestinal Tolerance of Low, Medium and High Dose Acute Oral l-Glutamine Supplementation in Healthy Adults: A Pilot Study. Nutrients. 2020;12(10):2953. PubMed
Vitamin B6 32 references
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Geerling BJ, Dagnelie PC, Badart-Smook A, et al. Diet as a risk factor for the development of ulcerative colitis. Am J Gastroenterol 2000;95:1008-13. PubMed
- South M. Neonatal seizures after pyridoxine use -- reply. Lancet 1999;354:2083. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Baxter P, Aicardi J. Neonatal seizures after pyridoxine use. Lancet 1999;354:2082-3. PubMed
- Bendich A, Cohen M. Vitamin B6 safety issues. Ann N Y Acad Sci 1990;585:321-30.
- Schaumburg H, Kaplan J, Windebank A. Sensory neuropathy from pyridoxine abuse. A new megavitamin syndrome. N Engl J Med 1983;309:445-8. PubMed
- Gordon N. Pyridoxine dependency: an update. Dev Med Child Neurol 1997;39:63-5. PubMed
- Lewis PJ. Pain in the hand and wrist. Pyridoxine supplements may help patients with carpal tunnel syndrome. BMJ 1995;310:1534. PubMed
- Kaufman G. Pyridoxine against amiodarone-induced photosensitivity (letter). Lancet 1984;1:51-2. PubMed
- Mulrow JP, Mulrow CD, McKenna WJ. Pyridoxine and amiodarone-induced photosensitivity. Ann Intern Med 1985;103:68-9. PubMed
- Kawada A, Kashima A, Shiraishi H, et al. Pyridoxine-induced photosensitivity and hypophosphatasia. Dermatology 2000;201:356-60.. PubMed
- Vasile A, Goldberg R, Kornberg B. Pyridoxine toxicity: report of a case. J Am Osteopath Assoc 1984;83:790-1. DOI
- Hansson O, Sillanpaa M. Pyridoxine and serum concentration of phenytoin and phenobarbitone. Lancet 1976;1:256. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Chittumma P, Kaewkiattikun K, Wiriyasiriwach B. Comparison of the effectiveness of ginger and vitamin B6 for treatment of nausea and vomiting in early pregnancy: a randomized double-blind controlled trial. J Med Assoc Thai 2007;90:15-20.
- Hatzitolios, A., Iliadis, F., Katsiki, N., and Baltatzi, M. Is the anti-hypertensive effect of dietary supplements via aldehydes reduction evidence based? A systematic review. Clin Exp.Hypertens. 2008;30(7):628-639. PubMed
- Vasdev, S., Ford, C. A., Parai, S., Longerich, L., and Gadag, V. Dietary vitamin B6 supplementation attenuates hypertension in spontaneously hypertensive rats. Mol.Cell Biochem. 1999;200(1-2):155-162.
- de, Vogel S., Dindore, V., van, Engeland M., Goldbohm, R. A., van den Brandt, P. A., and Weijenberg, M. P. Dietary folate, methionine, riboflavin, and vitamin B-6 and risk of sporadic colorectal cancer. J Nutr 2008;138(12):2372-2378. PubMed
- Hagen, I., Nesheim, B. I., and Tuntland, T. No effect of vitamin B-6 against premenstrual tension. A controlled clinical study. Acta Obstet.Gynecol.Scand. 1985;64(8):667-670. PubMed
- Aybak, M., Sermet, A., Ayyildiz, M. O., and Karakilcik, A. Z. Effect of oral pyridoxine hydrochloride supplementation on arterial blood pressure in patients with essential hypertension. Arzneimittelforschung. 1995;45(12):1271-1273.
- Lal, K. J., Dakshinamurti, K., and Thliveris, J. The effect of vitamin B6 on the systolic blood pressure of rats in various animal models of hypertension. J Hypertens. 1996;14(3):355-363. PubMed
- Lauritzen CH, Reuter HD, Repges R, Bohnert K, and Schmidt U. Treatment of premenstrual tension syndrome with Vitex agnus castus. Controlled, double-blind study versus pyridoxine. Phytomed 1997;4(3):183-189. PubMed
- Fonseca VA, Lavery LA, Thethi TK, et al. Metanx in type 2 diabetes with peripheral neuropathy: A randomized trial. Am J Med 2013;126(2):141-9. PubMed
- Hankey GJ, Eikelboom JW, Yi Q, et al. Treatment with B vitamins and incidence of cancer in patients with previous stroke or transient ischemic attack: Results of a randomized placebo-controlled trial. Stroke 2012;43(6):1572-7. PubMed
- Hoyer-Kuhn H, Kohbrok S, Volland R, Franklin J, Hero B, Beck BB, Hoppe B. Vitamin B6 in primary hyperoxaluria I: first prospective trial after 40 years of practice. Clin J Am Soc Nephrol. 2014 Mar;9(3):468-77. PubMed
- Mahmoud A, Tabassum S, Al Enazi S, et al. Amelioration of levetiracetam-induced behavioral side effects by pyridoxine. A randomized double blind controlled study. Pediatr Neurol 2021;119:15-21. PubMed
- Gupta M, Gallante B, Bamberger JN, et al. Prospective randomized evaluation of idiopathic hyperoxaluria treatments. J Endourol 2021;35(12):1844-1851. PubMed
- Li H, Chen M, Liang S, et al. Excessive vitamin B6 during treatment is related to poor prognosis of patients with nasopharyngeal carcinoma: A U-shaped distribution suggests low dose supplement. Clin Nutr 2021;40(4):2293-2300. PubMed
- Tanigawa J, Nabatame S, Tominaga K, et al. High-dose pyridoxine treatment for inherited glycosylphosphatidylinositol deficiency. Brain Dev 2021;43(6):680-687. PubMed
- Committee on Practice Bulletins-Obstetrics. ACOG Practice Bulletin No. 189: Nausea And Vomiting Of Pregnancy. Obstet Gynecol. 2018;131(1):e15-e30. PubMed
Folic Acid 56 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Duhra P. Treatment of gastrointestinal symptoms associated with methotrexate therapy for psoriasis. J Am Acad Dermatol 1993;28:466-9. PubMed
- Morgan SL, Baggott JE, Vaughn WH, et al. Supplementation with folic acid during methotrexate therapy for rheumatoid arthritis. A double-blind, placebo-controlled trial. Ann Intern Med 1994;121:833-41. PubMed
- Froscher W, Maier V, Laage M, et al. Folate deficiency, anticonvulsant drugs, and psychiatric morbidity. Clin Neuropharmacol 1995;18:165-82. PubMed
- Lewis DP, Van Dyke DC, Willhite LA, et al. Phenytoin-folic acid interaction. Ann Pharmacother 1995;29:726-35. PubMed
- Berg MJ, Stumbo PJ, Chenard CA, et al. Folic acid improves phenytoin pharmacokinetics. J Am Diet Assoc 1995;95:352-6. PubMed
- Berg MJ, Fincham RW, Ebert BE, et al. Phenytoin pharmacokinetics: Before and after folic acid administration. Epilepsia 1992;33:712-20. PubMed
- Shafer RB, Nuttall FQ. Calcium and folic acid absorption in patients taking anticonvulsant drugs. J Clin Endocrinol Metab 1975;41:1125-9. PubMed
- Leeb BF, Witzmann G, Ogris E, et al. Folic acid and cyanocobalamin levels in serum and erythrocytes during low-dose methotrexate therapy of rheumatoid arthritis and psoriatic arthritis patients. Clin Exp Rheumatol 1995;13:459-63.
- Morgan SL, Baggott JE, Lee JY, Alarcón GS. Folic acid supplementation prevents deficient blood folate levels and hyperhomocysteinemia during longterm, low dose methotrexate therapy for rheumatoid arthritis: implications for cardiovascular disease preventi
- Dijkmans BA. Folate supplementation and methotrexate. Br J Rheumatol 1995;34:1172-4. PubMed
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Lambie DG, Johnson RH. Drugs and folate metabolism. Drugs 1985;30:145-55. PubMed
- Amer College of Rheumatology ad hoc committee on clinical guidelines. Guidelines for monitoring drug therapy in rheumatoid arthritis. Arthritis Rheum 1996;39:723-31. DOI
- Suitor CW, Bailey LB. Dietary folate equivalents: interpretation and application. J Am Diet Assoc 2000;100:88-94. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Sandoval M, Charbonnet RM, Okuhama NN, et al. Cat's claw inhibits TNFalpha production and scavenges free radicals: role in cytoprotection. Free Radic Biol Med 2000;29:71-78.
- Antony AC. Megaloblastic Anemias. In: Hoffman R, Benz Jr EJ, Shattil SJ, et al. Hematology: Basic Principles and Practice. 3rd ed. New York, NY: Churchill Livingstone 2000: 451-79.
- Reynolds EH. Neurological aspects of folate and vitamin B12 metabolism. Clin Haematol 1976;5:661-96. DOI
- Reynolds EH. Folate metabolism and anticonvulsant therapy. Proc R Soc Med 1974;67:68.
- Ortiz Z, Shea B, Suarez Almazor M, et al. Folic acid and folinic acid for reducing side effects in patients receiving methotrexate for rheumatoid arthritis (Cochrane Review). Cochrane Database Syst Rev 2000;2:CD000951. PubMed
- Van Delden C, Hirschel B. Folinic acid supplements to pyrimethamine-sulfadiazine for Toxoplasma encephalitis are associated with better outcome (letter). J Infect Dis 1996;173:1294-5. PubMed
- Schroder H, Clausen N, Ostergard E, Pressler T. Folic acid supplements in vitamin tablets: a determinant of hematological drug tolerance in maintenance therapy of childhood acute lymphoblastic leukemia. Ped Hematol Oncol 1986;3:241-7. PubMed
- Lange H, Suryapranata H, De Luca G, et al. Folate therapy and in-stent restenosis after coronary stenting. N Engl J Med 2004;350:2673-81. PubMed
- Morris MC, Evans DA, Bienias JL, et al. Dietary folate and vitamin B12 intake and cognitive decline among community-dwelling older persons. Arch Neurol 2005;62:641-5. PubMed
- Bonaa KH, Njolstad I, Ueland PM, et al. NORVIT: Homocysteine lowering and cardiovascular events after acute myocardial infarction. N Enlg J Med 2006;354:1578-88. PubMed
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Figueiredo JC, Grau MV, Haile RW, et al. Folic acid and risk of prostate cancer: Results from a randomized clinical trial. J Natl Cancer Inst 2009;101:432-5. PubMed
- Clippe C, Freyer G, Milano G, Trillet-Lenoir V. Lethal toxicity of capecitabine due to abusive folic acid prescription. Clin Oncol (R Coll Radiol) 2003;15:299-300. PubMed
- Bedford Laboratories. Leucovorin calcium [package insert]. Bedford, OH. September 2008. Available at: http://www.bedfordlabs.com/BedfordLabsWeb/products/inserts/LCV-P02.pdf.
- Ebbing M, Bonaa KH, Nygard O, et al. Cancer incidence and mortality after treatment with folic acid and vitamin B12. JAMA 2009;302:2119-26.
- Haberg, S. E., London, S. J., Stigum, H., Nafstad, P., and Nystad, W. Folic acid supplements in pregnancy and early childhood respiratory health. Arch Dis.Child 2009;94(3):180-184. PubMed
- Whitrow, M. J., Moore, V. M., Rumbold, A. R., and Davies, M. J. Effect of supplemental folic acid in pregnancy on childhood asthma: a prospective birth cohort study. Am J Epidemiol. 12-15-2009;170(12):1486-1493. PubMed
- Collin, S. M., Metcalfe, C., Refsum, H., Lewis, S. J., Zuccolo, L., Smith, G. D., Chen, L., Harris, R., Davis, M., Marsden, G., Johnston, C., Lane, J. A., Ebbing, M., Bonaa, K. H., Nygard, O., Ueland, P. M., Grau, M. V., Baron, J. A., Donovan, J. L., Nea
- Baggott, J. E., Oster, R. A., and Tamura, T. Meta-analysis of cancer risk in folic acid supplementation trials. Cancer Epidemiol. 2012;36(1):78-81. PubMed
- Fonseca VA, Lavery LA, Thethi TK, et al. Metanx in type 2 diabetes with peripheral neuropathy: A randomized trial. Am J Med 2013;126(2):141-9. PubMed
- Hankey GJ, Eikelboom JW, Yi Q, et al. Treatment with B vitamins and incidence of cancer in patients with previous stroke or transient ischemic attack: Results of a randomized placebo-controlled trial. Stroke 2012;43(6):1572-7. PubMed
- Taneja S, Strand TA, Kumar T, et al. Folic acid and vitamin B-12 supplementation and common infections in 6-30-mo-old children in India: a randomized placebo-controlled trial. Am J Clin Nutr 2013;98(3):731-7. PubMed
- van Wijngaarden JP, Swart KM, Enneman AW, et al. Effect of daily vitamin B-12 and folic acid supplementation on fracture incidence in elderly individuals with an elevated plasma homocysteine concentration: B-PROOF, a randomized controlled trial. Am J Clin
- Qin X, Fan F, Cui Y, Chen F, Chen Y, Cheng X, Li Y, Wang B, Xu X, Xu X, Huo Y, Wang X. Folic acid supplementation with and without vitamin B6 and revascularization risk: a meta-analysis of randomized controlled trials. Clin Nutr. 2014;33(4):603-12. PubMed
- Crider KS, Cordero AM, Qi YP, Mulinare J, Dowling NF, Berry RJ. Prenatal folic acid and risk of asthma in children: a systematic review and meta-analysis. Am J Clin Nutr. 2013;98(5):1272-81. PubMed
- Matsubara S, Imai K, Murayama K, Higashizawa T. Severe liver dysfunction during nausea and vomiting of pregnancy: folic acid supplement as a suggested culprit. J Obstet Gynaecol. 2012;32(7):701-2. PubMed
- Qin X, Cui Y, Shen L, Sun N, Zhang Y, Li J, Xu X, Wang B, Xu X, Huo Y, Wang X. Folic acid supplementation and cancer risk: a meta-analysis of randomized controlled trials. Int J Cancer. 2013 1;133(5):1033-41. PubMed
- Tio M, Andrici J, Cox MR, Eslick GD. Folate intake and the risk of prostate cancer: a systematic review and meta-analysis. Prostate Cancer Prostatic Dis. 2014;17(3):213-9. PubMed
- Tomaszewski JJ, Richman EL, Sadetsky N, O'Keefe DS, Carroll PR, Davies BJ, Chan JM. Impact of folate intake on prostate cancer recurrence following definitive therapy: data from CaPSURE. J Urol. 2014;191(4):971-6. PubMed
- Valera-Gran D, García de la Hera M, Navarrete-Muñoz EM, Fernandez-Somoano A, Tardón A, Julvez J, Forns J, Lertxundi N, Ibarluzea JM, Murcia M, Rebagliato M, Vioque J; Infancia y Medio Ambiente (INMA) Project. Folic acid supplements during pregnancy and ch
- Van Der Woude DA, De Vries J, Van Wijk EM, Verzijl JM, Pijnenborg JM. A randomized controlled trial examining the addition of folic acid to iron supplementation in the treatment of postpartum anemia. Int J Gynaecol Obstet. 2014;126(2):101-5. PubMed
- Vila-Nova C, Wehby GL, Queirós FC, Chakraborty H, Félix TM, Goco N, Moore J, Gewehr EV, Lins L, Affonso CM, Murray JC. Periconceptional use of folic acid and risk of miscarriage - findings of the Oral Cleft Prevention Program in Brazil. J Perinat Med. 201 PubMed
- Vollset SE, Clarke R, Lewington S, Ebbing M, Halsey J, Lonn E, Armitage J, Manson JE, Hankey GJ, Spence JD, Galan P, Bønaa KH, Jamison R, Gaziano JM, Guarino P, Baron JA, Logan RF, Giovannucci EL, den Heijer M, Ueland PM, Bennett D, Collins R, Peto R; B-V
- Wehby GL, Félix TM, Goco N, Richieri-Costa A, Chakraborty H, Souza J, Pereira R, Padovani C, Moretti-Ferreira D, Murray JC. High dosage folic acid supplementation, oral cleft recurrence and fetal growth. Int J Environ Res Public Health. 2013 4;10(2):590-6 PubMed
- Fanidi A, Carreras-Torres R, Larose TL, et al. Is high vitamin B12 status a cause of lung cancer? Int J Cancer. 2019 Sep 15;145(6):1499-1503. PubMed
- Liu J, Li Z, Ye R, Liu J, Ren A. Periconceptional folic acid supplementation and risk of parent-reported asthma in children at 4-6 years of age. ERJ Open Res. 2020;6(1):00250-2019. PubMed
- Houghton LA, Sherwood KL, Pawlosky R, Ito S, O'Connor DL. [6S]-5-Methyltetrahydrofolate is at least as effective as folic acid in preventing a decline in blood folate concentrations during lactation. Am J Clin Nutr. 2006 Apr;83(4):842-50. PubMed
- Houghton LA, Yang J, O'Connor DL. Unmetabolized folic acid and total folate concentrations in breast milk are unaffected by low-dose folate supplements. Am J Clin Nutr. 2009 Jan;89(1):216-20. PubMed
- Chan SL, Chan AWH, Mo F, et al. Association Between Serum Folate Level and Toxicity of Capecitabine During Treatment for Colorectal Cancer. Oncologist. 2018 Dec;23(12):1436-1445. PubMed
- Sarris J, Ravindran A, Yatham LN, et al. Clinician guidelines for the treatment of psychiatric disorders with nutraceuticals and phytoceuticals: The World Federation of Societies of Biological Psychiatry (WFSBP) and Canadian Network for Mood and Anxiety T
Vitamin B12 30 references
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Hartman TJ, Woodson K, Stolzenberg-Solomon R, et al. Association of the B-vitamins pyridoxal 5'-phosphate (B6), B12, and folate with lung cancer risk in older men. Am J Epidemiol 2001;153:688-94.. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Lange H, Suryapranata H, De Luca G, et al. Folate therapy and in-stent restenosis after coronary stenting. N Engl J Med 2004;350:2673-81. PubMed
- Collin, S. M., Metcalfe, C., Refsum, H., Lewis, S. J., Zuccolo, L., Smith, G. D., Chen, L., Harris, R., Davis, M., Marsden, G., Johnston, C., Lane, J. A., Ebbing, M., Bonaa, K. H., Nygard, O., Ueland, P. M., Grau, M. V., Baron, J. A., Donovan, J. L., Nea
- Geissbuhler, P., Mermillod, B., and Rapin, C. H. Elevated serum vitamin B12 levels associated with CRP as a predictive factor of mortality in palliative care cancer patients: a prospective study over five years. J.Pain Symptom.Manage. 2000;20(2):93-103. PubMed
- Salles, N., Herrmann, F., Sakbani, K., Rapin, C. H., and Sieber, C. High vitamin B12 level: a strong predictor of mortality in elderly inpatients. J Am Geriatr.Soc 2005;53(5):917-918.
- Looker, H. C., Fagot-Campagna, A., Gunter, E. W., Pfeiffer, C. M., Sievers, M. L., Bennett, P. H., Nelson, R. G., Hanson, R. L., and Knowler, W. C. Homocysteine and vitamin B(12) concentrations and mortality rates in type 2 diabetes. Diabetes Metab Res R
- Uhl, W., Nolting, A., Golor, G., Rost, K. L., and Kovar, A. Safety of hydroxocobalamin in healthy volunteers in a randomized, placebo-controlled study. Clin Toxicol (Phila) 2006;44 Suppl 1:17-28. PubMed
- Borron, S. W., Baud, F. J., Barriot, P., Imbert, M., and Bismuth, C. Prospective study of hydroxocobalamin for acute cyanide poisoning in smoke inhalation. Ann Emerg.Med 2007;49(6):794-801, 801. PubMed
- Borron, S. W., Baud, F. J., Megarbane, B., and Bismuth, C. Hydroxocobalamin for severe acute cyanide poisoning by ingestion or inhalation. Am J Emerg.Med 2007;25(5):551-558. PubMed
- Lewis, J. G. Gout, Steatorrhoea, and Megaloblastic Anaemia. Ann Rheum.Dis 1962;21(3):284-286. PubMed
- Tal, S., Shavit, Y., Stern, F., and Malnick, S. Association between vitamin B12 levels and mortality in hospitalized older adults. J Am Geriatr.Soc 2010;58(3):523-526. PubMed
- Baztan, J. J., Gavidia, J. J., Gomez-Pavon, J., Esteve, A., and Ruiperez, I. High vitamin B12 levels and in-hospital mortality. J Am Geriatr.Soc 2010;58(11):2237-2238. PubMed
- Omboni, E., Checchini, M., and Longoni, F. [Hypopotassemia and megaloblastic anemia. Presentation of a case]. Minerva Med 8-31-1987;78(16):1255-1257.
- Aalfs As, Scholvinck LH, Horvath B. Acneiform eruption in a 5-year old due to vitamin B12 supplementation. Eur J Dermatol 2013;23(5):726-7. PubMed
- Balta I, Ozuguz P. Vitamin B12-induced acneiform eruption. Cutan Ocul Toxicol 2014;33(2):94-5. PubMed
- Carman KB, Belgemen T, Yis U. Involuntary movements misdiagnosed as seizure during vitamin B12 treatment. Pediatr Emerg Care 2013;29(11):1223-4. PubMed
- Djuric V, Bogic M, Popadic AP, et al. Anaphylactic reaction to hydroxycobalamin with tolerance to cyanocobalamin. Ann Allergy Asthma Immunol 2012;108(3):207-8. PubMed
- Kartel O, Gulec M, Demirel F, et al. Vitamin B12 allergy and successful desensitization with cyanocobalamin: A case report. Allergol Immunopath (Madr) 2012;40(5):324-5.
- Patiroglu T, Unal E, Yildirim S. Infantile tremor syndrome associated with cobalamin therapy: A case report. Clin Neurol Neurosurg 2013;115(9):1903-5. PubMed
- Schulte S, Barkema LW, Kardaun SH. Long-lasting atypical acneiform eruption with prominent comedones induced by hydroxocobalamin (vitamin B12). J Dtsch Dermatol Ges 2014;12(6):502-3.
- Zanus C, Alberini E, Costa P, et al. Involuntary movements after correction of vitamin B12 deficiency: A video-case report. Epileptic Disord 2012;14(2):174-80. PubMed
- Fanidi A, Carreras-Torres R, Larose TL, et al. Is high vitamin B12 status a cause of lung cancer? Int J Cancer. 2019 Sep 15;145(6):1499-1503. PubMed
- Fujita Y, Mizukami T, Maya Y, et al. Vitamin B12 allergy manifesting as lymphomatoid contact dermatitis. Eur J Dermatol. 2020;30(3):304-305. PubMed
- Dépret F, Hoffmann C, Daoud L, et al. Association between hydroxocobalamin administration and acute kidney injury after smoke inhalation: a multicenter retrospective study. Crit Care. 2019;23(1):421. PubMed
- Khairan P, Sobue T, Eshak ES, et al. Association of dietary intakes of vitamin B12, vitamin B6, folate, and methionine with the risk of esophageal cancer: the Japan Public Health Center-based (JPHC) prospective study. BMC Cancer 2021;21(1):982. PubMed
- Evans J, Pandya A, Ding Y, Qunibi WY. Hydroxocobalamin-Induced Oxalate Nephropathy in a Patient With Smoke Inhalation. Kidney Int Rep 2021;6(8):2228-2231. PubMed
- Lacombe V, Chabrun F, Lacout C, et al. Persistent elevation of plasma vitamin B12 is strongly associated with solid cancer. Sci Rep 2021;11(1):13361. PubMed
- Pegalajar-García MD, Cebolla-Verdugo M, Prados-Carmona Á, Llamas-Segura C, Navarro-Triviño FJ. Systemic allergic dermatitis to cobalt present in cyanocobalamin supplementation. Contact Dermatitis 2023;89(3):203-205. PubMed
Glycine 5 references
- Heresco-Levy U, Javitt DC, Ermilov M, et al. Efficacy of high-dose glycine in the treatment of enduring negative symptoms of schizophrenia. Arch Gen Psychiatry 1999;56:29-36.. PubMed
- Potkin SG, Jin Y, Bunney BG, Costa J, Gulasekaram B. Effect of clozapine and adjunctive high-dose glycine in treatment-resistant schizophrenia. Am J Psychiatry 1999;156:145-7.. PubMed
- Gusev EI, Skvortsova VI, Dambinova SA, et al. Neuroprotective effects of glycine for therapy of acute ischaemic stroke. Cerebrovasc Dis 2000;10:49-60. PubMed
- Inagawa K, Kawai N, Ono K, Sukegawa E, Tsubuku S, Takahashi M. Assessment of acute adverse effects of glycine ingestion at a high dose in human volunteers. Seikatsu Eisei. 2006; 50:27-32.
- Woods SW, Walsh BC, Hawkins KA, Miller TJ, Saksa JR, D'Souza DC, Pearlson GD, Javitt DC, McGlashan TH, Krystal JH. Glycine treatment of the risk syndrome for psychosis: report of two pilot studies. Eur Neuropsychopharmacol. 2013 Aug;23(8):931-40. PubMed
Riboflavin 5 references
- Schoenen J, Jacquy J, Lenaerts M. Effectiveness of high-dose riboflavin in migraine prophylaxis. A randomized controlled trial. Neurology 1998;50:466-70. PubMed
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Leeson LJ, Weidenheimer JF. Stability of tetracycline and riboflavin. J Pharm Sci. 1969;58(3):355-7. PubMed
- MacLennan, S. C., Wade, F. M., Forrest, K. M., Ratanayake, P. D., Fagan, E., and Antony, J. High-dose riboflavin for migraine prophylaxis in children: a double-blind, randomized, placebo-controlled trial. J Child Neurol. 2008;23(11):1300-1304.
- Dietary reference intakes (DRIs): estimated average requirements. Food and Nutrition Board, Institute of Medicine, National Academics. https://www.nal.usda.gov/sites/default/files/fnic_uploads//recommended_intakes_individuals.pdf Accessed July 24, 2017.
Vitamin C 51 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Back DJ, Breckenridge AM, MacIver M, et al. Interaction of ethinyloestradiol with ascorbic acid in man. Br Med J (Clin Res Ed) 1981;282:1516.
- Morris JC, Beeley L, Ballantine N. Interaction of ethinyloestradiol with ascorbic acid in man [letter]. Br Med J (Clin Res Ed) 1981;283:503.
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Dwyer JH, Merz NB, Shirocre AM, et al. Progression of early atherosclerosis and intake of vitamin C and vitamin E from supplements and food. The Los Angeles Atherosclerosis Study. 41st Annual Conference on Cardiovascular Disease Epidemiology and Prevent
- Levine M, Rumsey SC, Daruwala R, et al. Criteria and recommendations for vitamin C intake. JAMA 1999;281:1415-23. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Houston JB, Levy G. Drug biotransformation interactions in man VI: Acetaminophen and ascorbic acid. J Pharm Sci 1976;65:1218-21. PubMed
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Rosenthal G. Interaction of ascorbic acid and warfarin. JAMA 1971;215:1671. DOI
- Hume R, Johnstone JM, Weyers E. Interaction of ascorbic acid and warfarin. JAMA 1972;219:1479. DOI
- Smith EC, Skalski RJ, Johnson GC, Rossi GV. Interaction of ascorbic acid and warfarin. JAMA 1972;221:1166. DOI
- Traxer O, Huet B, Poindexter J, et al. Effect of ascorbic acid consumption on urinary stone risk factors. J Urol 2003;170:397-401.. PubMed
- Domingo JL, Gomez M, Llobet JM, Richart C. Effect of ascorbic acid on gastrointestinal aluminum absorption (letter). Lancet 1991;338:1467.
- Domingo JL, Gomez M, Llobet JM, Corbella J. Influence of some dietary constituents on aluminum absorption and retention in rats. Kidney Int 1991;39:598-601. PubMed
- Partridge NA, Regnier FE, White JL, Hem SL. Influence of dietary constituents on intestinal absorption of aluminum. Kidney Int 1989;35:1413-7. PubMed
- Mc Leod DC, Nahata MC. Inefficacy of ascorbic acid as a urinary acidifier (letter). N Engl J Med 1977;296:1413. DOI
- Hansten PD, Hayton WL. Effect of antacid and ascorbic acid on serum salicylate concentration. J Clin Pharmacol 1980;20:326-31. PubMed
- Dysken MW, Cumming RJ, Channon RA, Davis JM. Drug interaction between ascorbic acid and fluphenazine. JAMA 1979;241:2008. DOI
- Vihtamaki T, Parantainen J, Koivisto AM, et al. Oral ascorbic acid increases plasma oestradiol during postmenopausal hormone replacement therapy. Maturitas 2002;42:129-35. PubMed
- Slain D, Amsden JR, Khakoo RA, et al. Effect of high-dose vitamin C on the steady-state pharmacokinetics of the protease inhibitor indinavir in healthy volunteers. Pharmacotherapy 2005;25:165-70. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Feetam CL, Leach RH, Meynell MJ. Lack of a clinically important interaction between warfarin and ascorbic acid. Toxicol Appl Pharmacol 1975;31:544-7. PubMed
- Weintraub M, Griner PF. Warfarin and ascorbic acid: lack of evidence for a drug interaction. Toxicol Appl Pharmacol 1974;28:53-6. PubMed
- Lee DH, Folsom AR, Harnack L, et al. Does supplemental vitamin C increase cardiovascular disease risk in women with diabetes? Am J Clin Nutr 2004;80:1194-200. PubMed
- Taylor EN, Stampfer MJ, Curhan GC. Dietary factors and the risk of incident kidney stones in men: new insights after 14 years of follow-up. J Am Soc Nephrol 2004;15:3225-32. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Fairweather-Tait S, Hickson K, McGaw B, et al. Orange juice enhances aluminium absorption from antacid preparation. Eur J Clin Nutr. 1994;48(1):71-3.
- Gruenwald, J., Graubaum, H. J., Busch, R., and Bentley, C. Safety and tolerance of ester-C compared with regular ascorbic acid. Adv.Ther. 2006;23(1):171-178.
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Einerson, B., Nathorn, C., Kitiyakara, C., Sirada, M., and Thamlikitkul, V. The efficacy of ascorbic acid in suboptimal responsive anemic hemodialysis patients receiving erythropoietin: a meta-analysis. J Med.Assoc.Thai. 2011;94 Suppl 1:S134-S146.
- Li, G., Li, L., Yu, C., and Chen, L. Effect of vitamins C and E supplementation on Helicobacter pylori eradication: a meta-analysis. Br.J Nutr 2011;106(11):1632-1637.
- Chen X, Shen L, Gu X, et al. High-dose supplementation with vitamin C--induced pediatric urolithiasis: the first case report in a child and literature review. Urology. 2014;84(4):922-4. PubMed
- Sattar A, Willman JE, Kolluri R. Possible warfarin resistance due to interaction with ascorbic acid: case report and literature review. Am J Health Syst Pharm. 2013;70(9):782-6. PubMed
- Yaich S, Chaabouni Y, Charfeddine K, et al. Secondary oxalosis due to excess vitamin C intake: a cause of graft loss in a renal transplant recipient. Saudi J Kidney Dis Transpl. 2014;25(1):113-6. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Rumbold A, Ota E, Nagata C, Shahrook S, Crowther CA. Vitamin C supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004072. PubMed
- Seo MS, Kim JK, Shim JY. High-dose vitamin C promotes regression of multiple pulmonary metastases originating from hepatocellular carcinoma. Yonsei Med J. 2015;56(5):1449-52. PubMed
- Skelin M, Lucijanic T, Amidzic Klaric D, et al. Factors Affecting Gastrointestinal Absorption of Levothyroxine: A Review. Clin Ther. 2017 Feb;39(2):378-403. PubMed
- Jiang K, Tang K, Liu H, Xu H, Ye Z, Chen Z. Ascorbic acid supplements and kidney stones incidence among men and women: a systematic review and meta-analysis. Urol J. 2019;16(2):115-120.
- Thomas S, Patel D, Bittel B, et al. Effect of High-Dose Zinc and Ascorbic Acid Supplementation vs Usual Care on Symptom Length and Reduction Among Ambulatory Patients With SARS-CoV-2 Infection: The COVID A to Z Randomized Clinical Trial. JAMA Netw Open. 2 PubMed
- Giffen MA, McLemore JL. Hyperoxalosis Secondary to Intravenous Vitamin C Administration as a Non-Allopathic Treatment for Cancer. Acad Forensic Pathol 2019;9(1-2):118-126. PubMed
- Maike A, Sturgill D, Gallan A. Oxalate Nephropathy in a Renal Transplant Recipient After Receiving High Dose Ascorbic Acid. Am J Med Sci 2021. PubMed
- Shen ZY, Chen YR, Wang MC, Chang SS. High-dose vitamin C-induced acute oxalate nephropathy in a renal transplant recipient: a case report and literature review. Asian J Surg 2022. PubMed
- Yanase F, Spano S, Maeda A, et al. Mega-dose sodium ascorbate: a pilot, single-dose, physiological effect, double-blind, randomized, controlled trial. Crit Care 2023;27(1):371. PubMed
- Sharma Y, Sumanadasa S, Shahi R, et al. Efficacy and safety of vitamin C supplementation in the treatment of community-acquired pneumonia: a systematic review and meta-analysis with trial sequential analysis. Sci Rep 2024;14(1):11846. PubMed
- Pejcic AV, Petrovic NZ, Djordjic MD, Milosavljevic MN. Vitamin C Levels in Pregnant Women and the Efficacy of Vitamin C Supplements in Preventing Premature Rupture of Membranes: A Systematic Review and Meta-Analysis. Balkan Med J 2024;41(4):248-260. PubMed
Niacin 66 references
- Garg R, Malinow MR, Pettinger M, et al. Niacin treatment increases plasma homocysteine levels. Am Heart J 1999;138:1082-7.
- Anon. Inositol hexaniacinate. Altern Med Rev 1998;3:222-3.
- Knodel LC, Talbert RL. Adverse effects of hypolipidaemic drugs. Med Toxicol 1987;2:10-32. PubMed
- Guyton JR, Blazing MA, Hagar J, et al. Extended-release niacin vs gemfibrozil for the treatment of low levels of high-density lipoprotein cholesterol. Niaspan-Gemfibrozil Study Group. Arch Intern Med 2000;160:1177-84. PubMed
- Gibbons LW, Gonzalez V, Gordon N, Grundy S. The prevalence of side effects with regular and sustained-release nicotinic acid. Am J Med 1995;99:378-85. PubMed
- Whelan AM, Price SO, Fowler SF, Hainer BL. The effect of aspirin on niacin-induced cutaneous reactions. J Fam Pract 1992;34:165-8.
- Jungnickel PW, Maloley PA, Vander Tuin EL, et al. Effect of two aspirin pretreatment regimens on niacin-induced cutaneous reactions. J Gen Intern Med 1997;12:591-6. PubMed
- Capuzzi DM, Guyton JR, Morgan JM, et al. Efficacy and safety of an extended-release niacin (Niaspan): a long-term study. Am J Cardiol 1998;82:74-81;disc. 85U-6U. PubMed
- Gray DR, Morgan T, Chretien SD, Kashyap ML. Efficacy and safety of controlled-release niacin in dyslipoproteinemic veterans. Ann Intern Med 1994;121:252-8. PubMed
- McKenney JM, Proctor JD, Harris S, Chinchili VM. A comparison of the efficacy and toxic effects of sustained- vs immediate-release niacin in hypercholesterolemic patients. JAMA 1994;271:672-7. DOI
- Knopp RH, Alagona P, Davidson M, et al. Equivalent efficacy of a time-release form of niacin (Niaspan) given once-a-night versus plain niacin in the management of hyperlipidemia. Metabolism 1998;47:1097-104. PubMed
- Knopp RH. Clinical profiles of plain versus sustained-release niacin (Niaspan) and the physiologic rationale for nighttime dosing. Am J Cardiol 1998;82:24U-28U;discussion 39U-41U. PubMed
- Garg A, Grundy SM. Nicotinic acid as therapy for dyslipidemia in non-insulin-dependent diabetes mellitus. JAMA 1990;264:723-6. DOI
- Leighton RF, Gordon NF, Small GS, et al. Dental and gingival pain as side effects of niacin therapy. Chest 1998;114:1472-4. PubMed
- American Society of Health-System Pharmacists. ASHP Therapeutic Position Statement on the safe use of niacin in the management of dyslipidemias. Am J Health Syst Pharm 1997;54:2815-9. DOI
- Vega GL, Grundy SM. Lipoprotein responses to treatment with lovastatin, gemfibrozil, and nicotinic acid in normolipidemic patients with hypoalphalipoproteinemia. Arch Intern Med 1994;154:73-82. DOI
- Guyton JR, Goldberg AC, Kreisberg RA, et al. Effectiveness of once-nightly dosing of extended-release niacin alone and in combination for hypercholesterolemia. Am J Cardiol 1998;82:737-43.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Bays HE, Dujovne CA. Drug interactions of lipid-altering drugs. Drug Saf 1998;19:355-71. PubMed
- Rader JI, Calvert RJ, Hathcock JN. Hepatic toxicity of unmodified and time-release preparations of niacin. Am J Med 1992;92:77-81. PubMed
- Kahn SE, Beard JC, Schwartz MW, et al. Increased B-cell secretory capacity as mechanism for islet adaptation to nicotinic acid-induced insulin resistance. Diabetes 1989;38:562-8.
- Schwartz ML. Severe reversible hyperglycemia as a consequence of niacin therapy. Arch Int Med 1993;153:2050-2. DOI
- Raising HDL and Niacin Use. Pharmacist's Letter/Prescriber's Letter 2004;20(5):200504.
- McKenney J. New perspectives on the use of niacin in the treatment of lipid disorders. Arch Intern Med 2004;164:697-705. PubMed
- Reaven P, Witztum JL. Lovastatin, nicotinic acid and rhabdomyolysis (letter). Ann Int Med 1988;109:597-8. PubMed
- Ito MK. Advances in the understanding and management of dyslipidemia: using niacin-based therapies. Am J Health-Syst Pharm 2003;60(suppl 2):s15-21. PubMed
- Schwab RA, Bachhuber BH. Delirium and lactic acidosis caused by ethanol and niacin coingestion. Am J Emerg Med 1991;9:363-5. PubMed
- Product information: Niaspan. Kos Pharmaceuticals. Cranbury, NJ. 2005. Available at www.niaspan.com/professional/content/pdfs/productinfo.pdf. (Accessed 3 March 2006).
- Ding RW, Kolbe K, Merz B, et al. Pharmacokinetics of nicotinic acid-salicylic acid interaction. Clin Pharmacol Ther 1989;46:642-7. PubMed
- NIH News. NIH stops clinical trial on combination cholesterol treatment. May 26, 2011. http://www.nih.gov/news/health/may2011/nhlbi-26.htm. (Accessed 3 June 2011).
- Dearing BD, Lavie CJ, Lohmann TP, Genton E. Niacin-induced clotting factor synthesis deficiency with coagulopathy. Arch Intern Med. 1992;152(4):861-3. DOI
- O'Brien T, Silverberg JD, Nguyen TT. Nicotinic acid-induced toxicity associated with cytopenia and decreased levels of thyroxine-binding globulin. Mayo Clin Proc. 1992;67(5):465-8. PubMed
- Gadegbeku CA, Dhandayuthapani A, Shrayyef MZ, Egan BM. Hemodynamic effects of nicotinic acid infusion in normotensive and hypertensive subjects. Am J Hypertens. 2003;16(1):67-71. PubMed
- Garnett WR. Interactions with hydroxymethylglutaryl-coenzyme A reductase inhibitors. Am J Health Syst Pharm. 1995;52(15):1639-45. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Dunn RT, Ford MA, Rindone JP, Kwiecinski FA. Low-Dose Aspirin and Ibuprofen Reduce the Cutaneous Reactions Following Niacin Administration. Am J Ther. 1995;2(7):478-480. PubMed
- Cashin-Hemphill L, Spencer CA, Nicoloff JT, et al. Alterations in serum thyroid hormonal indices with colestipol-niacin therapy. Ann Intern Med. 1987;107(3):324-9. PubMed
- Drinka PJ. Alterations in thyroid and hepatic function tests associated with preparations of sustained-release niacin. Mayo Clin Proc. 1992;67(12):1206. PubMed
- Shakir KM, Kroll S, Aprill BS, Drake AJ 3rd, Eisold JF. Nicotinic acid decreases serum thyroid hormone levels while maintaining a euthyroid state. Mayo Clin Proc. 1995;70(6):556-8. PubMed
- Etchason JA, Miller TD, Squires RW, et al. Niacin-induced hepatitis: a potential side effect with low-dose time-release niacin. Mayo Clin Proc. 1991;66(1):23-8. PubMed
- Henkin Y, Johnson KC, Segrest JP. Rechallenge with crystalline niacin after drug-induced hepatitis from sustained-release niacin. JAMA. 1990;264(2):241-3. DOI
- Henkin Y, Oberman A, Hurst DC, Segrest JP. Niacin revisited: clinical observations on an important but underutilized drug. Am J Med. 1991;91(3):239-46. PubMed
- Brown BG, Bardsley J, Poulin D, et al. Moderate dose, three-drug therapy with niacin, lovastatin, and colestipol to reduce low-density lipoprotein cholesterol <100 mg/dl in patients with hyperlipidemia and coronary artery disease. Am J Cardiol. 1997;80(2)
- Goldberg A, Alagona P Jr, Capuzzi DM, et al. Multiple-dose efficacy and safety of an extended-release form of niacin in the management of hyperlipidemia. Am J Cardiol. 2000;85(9):1100-5. PubMed
- Aronov DM, Keenan JM, Akhmedzhanov NM, et al. Clinical trial of wax-matrix sustained-release niacin in a Russian population with hypercholesterolemia. Arch Fam Med. 1996;5(10):567-75. PubMed
- Morgan JM, Capuzzi DM, Guyton JR, et al. Treatment Effect of Niaspan, a Controlled-release Niacin, in Patients With Hypercholesterolemia: A Placebo-controlled Trial. J Cardiovasc Pharmacol Ther. 1996;1(3):195-202. PubMed
- Andersson RG, Aberg G, Brattsand R, Ericsson E, Lundholm L. Studies on the mechanism of flush induced by nicotinic acid. Acta Pharmacol Toxicol (Copenh). 1977 Jul;41(1):1-10. PubMed
- Brown WV. Niacin for lipid disorders. Indications, effectiveness, and safety. Postgrad Med. 1995 Aug;98(2):185-9, 192-3. PubMed
- O'REILLY PO, CALLBECK MJ, HOFFER A. Sustained-release nicotinic acid (nicospan); effect on (1) cholesterol levels and (2) leukocytes. Can Med Assoc J. 1959;80(5):359-62.
- Gharavi AG, Diamond JA, Smith DA, Phillips RA. Niacin-induced myopathy. Am J Cardiol. 1994;74(8):841-2. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Fraunfelder FW, Fraunfelder FT, Illingworth DR. Adverse ocular effects associated with niacin therapy. Br J Ophthalmol 1995;79:54-56. PubMed
- Ali EH, McJunkin B, Jubelirer S, Hood W. Niacin induced coagulopathy as a manifestation of occult liver injury. W V Med J. 2013 Jan-Feb;109(1):12-4
- Aramwit P, Srisawadwong R, Supasyndh O. Effectiveness and safety of extended-release nicotinic acid for reducing serum phosphorus in hemodialysis patients. J Nephrol. 2012 May-Jun;25(3):354-62. PubMed
- Bassan M. A case for immediate-release niacin. Heart Lung. 2012 Jan-Feb;41(1):95-8. PubMed
- Davidson MH, Rooney M, Pollock E, Drucker J, Choy Y. Effect of colesevelam and niacin on low-density lipoprotein cholesterol and glycemic control in subjects with dyslipidemia and impaired fasting glucose. J Clin Lipidol. 2013 Sep-Oct;7(5):423-32. PubMed
- Guyton JR, Fazio S, Adewale AJ, Jensen E, Tomassini JE, Shah A, Tershakovec AM. Effect of extended-release niacin on new-onset diabetes among hyperlipidemic patients treated with ezetimibe/simvastatin in a randomized controlled trial. Diabetes Care. 2012 PubMed
- Loebl T, Raskin S. A novel case report: acute manic psychotic episode after treatment with niacin. J Neuropsychiatry Clin Neurosci. 2013 Fall;25(4):E14. PubMed
- Teo KK, Goldstein LB, Chaitman BR, Grant S, Weintraub WS, Anderson DC, Sila CA, Cruz-Flores S, Padley RJ, Kostuk WJ, Boden WE; AIM-HIGH Investigators. Extended-release niacin therapy and risk of ischemic stroke in patients with cardiovascular disease: the
- Goldie C, Taylor AJ, Nguyen P, McCoy C, Zhao XQ, Preiss D. Niacin therapy and the risk of new-onset diabetes: a meta-analysis of randomized controlled trials. Heart. 2016 Feb;102(3):198-203.
- Schandelmaier S, Briel M, Saccilotto R, Olu KK, Arpagaus A, Hemkens LG, Nordmann AJ. Niacin for primary and secondary prevention of cardiovascular events. Cochrane Database Syst Rev. 2017 Jun 14;6:CD009744. PubMed
- Jenkins DJA, Spence JD, Giovannucci EL, et al. Supplemental vitamins and minerals for CVD prevention and treatment. J Am Coll Cardiol 2018;71(22):2570-84. PubMed
- Song S, Lee CJ, Oh J, Park S, Kang SM, Lee SH. Effect of Niacin on Carotid Atherosclerosis in Patients at Low-Density Lipoprotein-Cholesterol Goal but High Lipoprotein (a) Level: a 2-Year Follow-Up Study. J Lipid Atheroscler. 2019;8(1):58-66. PubMed
- Kimura H, Umemori Y, Yuki D. Anaphylactic shock-like symptoms due to niacin overdose: A case report. J Dermatol 2022;49(8):e287-e288. PubMed
- Nawaz N, Mistretta T, Karime C, Lewis J, Wolf E. Cholestatic Drug-Induced Liver Injury in a Patient Taking High-Dose Niacin for Hyperlipidemia. J Investig Med High Impact Case Rep 2024;12:23247096231224349. PubMed
Selenium 36 references
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Trafikowska U, Zachara BA, Wiacek M, et al. Selenium supply and glutathione peroxidase activity in breastfed Polish infants. Acta Paediatr 1996;85:1143-5. PubMed
- Duffield-Lillico AJ, Slate EH, Reid ME, et al. Selenium supplementation and secondary prevention of nonmelanoma skin cancer in a randomized trial. J Natl Cancer Inst 2003;95:1477-81.. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Schiavon R, Freeman GE, Guidi GC, et al. Selenium enhances prostacyclin production by cultured endothelial cells: possible explanation for increased bleeding times in volunteers taking selenium as a dietary supplement. Thromb Res 1984;34:389-96. PubMed
- Davila JC, Edds GT, Osuna O, Simpson CF. Modification of the effects of aflatoxin B1 and warfarin in young pigs given selenium. Am J Vet Res 1983;44:1877-83. DOI
- Heese HD, Lawrence MA, Dempster WS, Pocock F. Reference concentrations of serum selenium and manganese in healthy nulliparas. S Afr Med J 1988;73:163-5.
- Lloyd B, Lloyd RS, Clayton BE. Effect of smoking, alcohol and other factors on the selenium status of a healthy population. J Epidemiol Commun Health 1983;37:213-7. PubMed
- Capel ID, Jenner M, Williams DC, et al. The effect of prolonged oral contraceptive steroid use on erythrocyte glutathione peroxidase activity. J Steroid Biochem 1981;14:729-32. PubMed
- Contempre B, Dumont JE, Ngo B, et al. Effect of selenium supplementation in hypothyroid subjects of an iodine and selenium deficient area: the possible danger of indiscriminate supplementation of iodine-deficient subjects with selenium. J Clin Endocrinol PubMed
- Hofbauer LC, Spitzweg C, Magerstadt RA, Heufelder AE. Selenium-induced thyroid dysfunction. Postgrad Med J 1997;73:103-4. PubMed
- Debski B, Milner JA. Dietary selenium supplementation prolongs pentobarbital induced hypnosis. J Nutr Biochem 2004;15:548-53. PubMed
- Ishikawa M, Sasaki M, Koiwai K, et al. Inhibition of hepatic mixed-function oxidase enzymes in mice by acute and chronic treatment with selenium. J Pharmacobiodyn 1992;15:377-85. PubMed
- Lippmann SM, Klein EA, Goodman PJ, et al. Effect of selenium and vitamin E on risk of prostate cancer and other cancers: the selenium and vitamin E cancer prevention trial (SELECT). JAMA 2009;301:39-51. DOI
- Reid SM, Middleton P, Cossich MC, Crowther CA. Interventions for clinical and subclinical hypothyroidism in pregnancy. Cochrane Database Syst Rev 2010;(7):CD007752. PubMed
- Vinceti, M., Wei, E. T., Malagoli, C., Bergomi, M., and Vivoli, G. Adverse health effects of selenium in humans. Rev.Environ.Health 2001;16(4):233-251. PubMed
- Abrams, C. K., Siram, S. M., Galsim, C., Johnson-Hamilton, H., Munford, F. L., and Mezghebe, H. Selenium deficiency in long-term total parenteral nutrition. Nutr Clin Pract 1992;7(4):175-178. PubMed
- Spiller, H. A. and Pfiefer, E. Two fatal cases of selenium toxicity. Forensic Sci Int 8-24-2007;171(1):67-72. PubMed
- Negro, R., Greco, G., Mangieri, T., Pezzarossa, A., Dazzi, D., and Hassan, H. The influence of selenium supplementation on postpartum thyroid status in pregnant women with thyroid peroxidase autoantibodies. J Clin Endocrinol.Metab 2007;92(4):1263-1268. PubMed
- Alexander, J. Selenium. Novartis.Found.Symp 2007;282:143-149.
- Salonen, J. T., Salonen, R., Seppanen, K., Rinta-Kiikka, S., Kuukka, M., Korpela, H., Alfthan, G., Kantola, M., and Schalch, W. Effects of antioxidant supplementation on platelet function: a randomized pair-matched, placebo-controlled, double-blind trial
- Kupka, R., Mugusi, F., Aboud, S., Msamanga, G. I., Finkelstein, J. L., Spiegelman, D., and Fawzi, W. W. Randomized, double-blind, placebo-controlled trial of selenium supplements among HIV-infected pregnant women in Tanzania: effects on maternal and chil
- Kamble, P., Mohsin, N., Jha, A., Date, A., Upadhaya, A., Mohammad, E., Khalil, M., Pakkyara, A., and Budruddin, M. Selenium intoxication with selenite broth resulting in acute renal failure and severe gastritis. Saudi.J Kidney Dis.Transpl. 2009;20(1):106
- Peretz, A., Neve, J., Desmedt, J., Duchateau, J., Dramaix, M., and Famaey, J. P. Lymphocyte response is enhanced by supplementation of elderly subjects with selenium-enriched yeast. Am.J Clin.Nutr. 1991;53(5):1323-1328. PubMed
- Kumpulainen, J., Salmenpera, L., Siimes, M. A., Koivistoinen, P., and Perheentupa, J. Selenium status of exclusively breast-fed infants as influenced by maternal organic or inorganic selenium supplementation. Am.J Clin.Nutr. 1985;42(5):829-835. PubMed
- Han, L. and Zhou, S. M. Selenium supplement in the prevention of pregnancy induced hypertension. Chin Med J (Engl) 1994;107(11):870-871.
- Kiremidjian-Schumacher, L., Roy, M., Wishe, H. I., Cohen, M. W., and Stotzky, G. Supplementation with selenium and human immune cell functions. II. Effect on cytotoxic lymphocytes and natural killer cells. Biol.Trace Elem.Res. 1994;41(1-2):115-127. PubMed
- Srivastava, A. K., Gupta, B. N., Bihari, V., and Gaur, J. S. Generalized hair loss and selenium exposure. Vet.Hum.Toxicol. 1995;37(5):468-469.
- Sudfeld CR, Aboud S, Kupka R, et al. Effect of selenium supplementation on HIV-1 RNA detection in breast milk of Tanzanian women. Nutrition 2014;30(9):1081-4. PubMed
- Rees K, Hartley L, Day C, et al. Selenium supplementation for the primary prevention of cardiovascular disease. Cochrane Database Syst Rev 2013;1:CD009671. PubMed
- Thompson PA, Ashbeck EL, Roe DJ, et al. Selenium Supplementation for Prevention of Colorectal Adenomas and Risk of Associated Type 2 Diabetes. J Natl Cancer Inst. 2016;108(12). PubMed
- Wichman J, Winther KH, Bonnema SJ, Hegedüs L. Selenium supplementation significantly reduces thyroid autoantibody levels in patients with chronic autoimmune thyroiditis: a systematic review and meta-analysis. Thyroid 2016;26(12):1681-92. PubMed
- Vinceti M, Filippini T, Rothman KJ. Selenium exposure and the risk of type 2 diabetes: a systematic review and meta-analysis. Eur J Epidemiol. 2018 Sep;33(9):789-810. Epub 2018 Jul 5. Review. PubMed
- Fallah S, Sani FV, Firoozrai M. Effect of contraceptive pill on the selenium and zinc status of healthy subjects. Contraception. 2009;80(1):40-3. PubMed
- Malpas CB, Vivash L, Genc S, et al. A Phase IIa Randomized Control Trial of VEL015 (Sodium Selenate) in Mild-Moderate Alzheimer's Disease. J Alzheimers Dis. 2016;54(1):223-232. PubMed
Taurine 21 references
- Ahmad S, Robertson HT, Golper TA, et al. Multicenter trial of L-carnitine in maintenance hemodialysis patients. II. Clinical and biochemical effects. Kidney Int 1990;38:912-8. PubMed
- Machado-Vieira R, Viale CI, Kapczinski F. Mania associated with an energy drink: the possible role of caffeine, taurine, and inositol. Can J Psychiatry 2001;46:454-5. PubMed
- Obermann M, Schorn CF, Mummel P, et al. Taurine induced toxic encephalopathy? Clin Neurol Neurosurg 2006;108:812-3. PubMed
- Bichler, A., Swenson, A., and Harris, M. A. A combination of caffeine and taurine has no effect on short term memory but induces changes in heart rate and mean arterial blood pressure. Amino Acids 2006;31(4):471-476. PubMed
- Iyadurai, S. J. and Chung, S. S. New-onset seizures in adults: possible association with consumption of popular energy drinks. Epilepsy Behav 2007;10(3):504-508. PubMed
- Berger, A. J. and Alford, K. Cardiac arrest in a young man following excess consumption of caffeinated "energy drinks". Med J Aust. 1-5-2009;190(1):41-43. PubMed
- Worthley, M. I., Prabhu, A., De, Sciscio P., Schultz, C., Sanders, P., and Willoughby, S. R. Detrimental effects of energy drink consumption on platelet and endothelial function. Am J Med 2010;123(2):184-187. PubMed
- Morchon, Simon D. and Perez Castrillon, J. L. [Hypoglycemia by intake of taurine]. Rev.Clin Esp. 2010;210(1):49.
- Livshits, Z., Hoffman, R. S., Hymes, K. B., and Nelson, L. S. If vitamins could kill: massive hemolysis following naturopathic vitamin infusion. J Med Toxicol. 2011;7(3):224-226. PubMed
- Schoffl, I., Kothmann, J. F., Schoffl, V., Rupprecht, H. D., and Rupprecht, T. "Vodka energy": too much for the adolescent nephron? Pediatrics 2011;128(1):e227-e231. PubMed
- Calabro, R. S., Italiano, D., Gervasi, G., and Bramanti, P. Single tonic-clonic seizure after energy drink abuse. Epilepsy Behav 2012;23(3):384-385. PubMed
- Fujita, T., Ando, K., Noda, H., Ito, Y., and Sato, Y. Effects of increased adrenomedullary activity and taurine in young patients with borderline hypertension. Circulation 1987;75(3):525-532. PubMed
- Darling, P. B., Lepage, G., Leroy, C., Masson, P., and Roy, C. C. Effect of taurine supplements on fat absorption in cystic fibrosis. Pediatr Res 1985;19(6):578-582. PubMed
- Fukuyama, Y. and Ochiai, Y. Therapeutic trial by taurine for intractable childhood epilepsies. Brain Dev. 1982;4(1):63-69. PubMed
- Franconi, F., Bennardini, F., Mattana, A., Miceli, M., Ciuti, M., Mian, M., Gironi, A., Anichini, R., and Seghieri, G. Plasma and platelet taurine are reduced in subjects with insulin-dependent diabetes mellitus: effects of taurine supplementation. Am.J. DOI
- Stohs SJ, Miller M. A case study involving allergic reactions to sulfur-containing compounds including, sulfite, taurine, acesulfame potassium and sulfonamides. Food Chem Toxicol. 2014 Jan;63:240-3. PubMed
- Sun Q, Wang B, Li Y, Sun F, et al. Taurine supplementation lowers blood pressure and improves vascular function in prehypertension: randomized, double-blind, placebo-controlled study. Hypertension 2016 Mar;67(3):541-9. PubMed
- Jang ES, Hwang SH, Kim JW, Jeong SH. Effectiveness of 4-week oral taurine treatment for muscle cramps in patients with liver cirrhosis: a single-arm pilot study. Yonsei Med J 2021;62(1):21-8. PubMed
- Guan L, Miao P. The effects of taurine supplementation on obesity, blood pressure and lipid profile: A meta-analysis of randomized controlled trials. Eur J Pharmacol 2020;885:173533. PubMed
- Higgins JP, Liras GN, Liras IN, et al. Energy Drink Effects on Hemodynamics and Endothelial Function in Young Adults. Cardiology. 2021;146(2):258-262. PubMed
- Pallangyo P, Bhalia SV, Komba M, et al. Acute Myocardial Infarction Following the Consumption of Energy Drink in a 28-Year-Old Male: A Case Report. J Investig Med High Impact Case Rep. 2023 Jan-Dec;11:23247096231168811. PubMed
Turmeric 102 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Sharma RA, McLelland HR, Hill KA, et al. Pharmacodynamic and pharmacokinetic study of oral Curcuma extract in patients with colorectal cancer. Clin Cancer Res 2001;7:1894-900..
- Shah BH, Nawaz Z, Pertani SA. Inhibitory effect of curcumin, a food spice from turmeric, on platelet-activating factor- and arachidonic acid-mediated platelet aggregation through inhibition of thromboxane formation and Ca2+ signaling. Biochem Pharmacol 1 PubMed
- Hata M, Sasaki E, Ota M, et al . Allergic contact dermatitis from curcumin (turmeric). Contact Dermatitis 1997;36:107-8. PubMed
- Kuttan R, Sudheeran PC, Josph CD. Turmeric and curcumin as topical agents in cancer therapy. Tumori 1987;73:29-31.. PubMed
- Thapliyal R, Deshpande SS, Maru GB. Mechanism(s) of turmeric-mediated protective effects against benzo(a)pyrene-derived DNA adducts. Cancer Lett 2002;175:79-88. PubMed
- Lee SW, Nah SS, Byon JS, et al. Transient complete atrioventricular block associated with curcumin intake. Int J Cardiol 2011;150:e50-2. PubMed
- Kuptniratsaikul V, Thanakhumtorn S, Chinswangwatanakul P, et al. Efficacy and safety of Curcuma domestica extracts in patients with knee osteoarthritis. J Altern Complement Med 2009;15:891-7.
- Carroll RE, Benya RV, Turgeon DK, et al. Phase IIa clinical trial of curcumin for the prevention of colorectal neoplasia. Cancer Prev Res (Phila) 2011;4:354-64. PubMed
- Junyaprasert, V. B., Soonthornchareonnon, N., Thongpraditchote, S., Murakami, T., and Takano, M. Inhibitory effect of Thai plant extracts on P-glycoprotein mediated efflux. Phytother.Res 2006;20(1):79-81. PubMed
- Ampasavate, C., Sotanaphun, U., Phattanawasin, P., and Piyapolrungroj, N. Effects of Curcuma spp. on P-glycoprotein function. Phytomedicine. 2010;17(7):506-512. PubMed
- Hou, X. L., Takahashi, K., Tanaka, K., Tougou, K., Qiu, F., Komatsu, K., Takahashi, K., and Azuma, J. Curcuma drugs and curcumin regulate the expression and function of P-gp in Caco-2 cells in completely opposite ways. Int.J Pharm 6-24-2008;358(1-2):224-2 PubMed
- Choi, B. H., Kim, C. G., Lim, Y., Shin, S. Y., and Lee, Y. H. Curcumin down-regulates the multidrug-resistance mdr1b gene by inhibiting the PI3K/Akt/NF kappa B pathway. Cancer Lett. 1-18-2008;259(1):111-118.
- Zhang, W., Tan, T. M., and Lim, L. Y. Impact of curcumin-induced changes in P-glycoprotein and CYP3A expression on the pharmacokinetics of peroral celiprolol and midazolam in rats. Drug Metab Dispos. 2007;35(1):110-115. PubMed
- Limtrakul, P., Chearwae, W., Shukla, S., Phisalphong, C., and Ambudkar, S. V. Modulation of function of three ABC drug transporters, P-glycoprotein (ABCB1), mitoxantrone resistance protein (ABCG2) and multidrug resistance protein 1 (ABCC1) by tetrahydrocu
- Holland, M. L., Panetta, J. A., Hoskins, J. M., Bebawy, M., Roufogalis, B. D., Allen, J. D., and Arnold, J. C. The effects of cannabinoids on P-glycoprotein transport and expression in multidrug resistant cells. Biochem.Pharmacol 4-14-2006;71(8):1146-1154 PubMed
- Tang, X. Q., Bi, H., Feng, J. Q., and Cao, J. G. Effect of curcumin on multidrug resistance in resistant human gastric carcinoma cell line SGC7901/VCR. Acta Pharmacol Sin. 2005;26(8):1009-1016. PubMed
- Nabekura, T., Kamiyama, S., and Kitagawa, S. Effects of dietary chemopreventive phytochemicals on P-glycoprotein function. Biochem.Biophys.Res Commun. 2-18-2005;327(3):866-870. PubMed
- Romiti, N., Tongiani, R., Cervelli, F., and Chieli, E. Effects of curcumin on P-glycoprotein in primary cultures of rat hepatocytes. Life Sci. 1998;62(25):2349-2358. PubMed
- Yue, G. G., Cheng, S. W., Yu, H., Xu, Z. S., Lee, J. K., Hon, P. M., Lee, M. Y., Kennelly, E. J., Deng, G., Yeung, S. K., Cassileth, B. R., Fung, K. P., Leung, P. C., and Lau, C. B. The role of turmerones on curcumin transportation and P-glycoprotein acti
- Shenouda, N. S., Zhou, C., Browning, J. D., Ansell, P. J., Sakla, M. S., Lubahn, D. B., and MacDonald, R. S. Phytoestrogens in common herbs regulate prostate cancer cell growth in vitro. Nutr.Cancer 2004;49(2):200-208. PubMed
- Appiah-Opong, R., Commandeur, J. N., Vugt-Lussenburg, B., and Vermeulen, N. P. Inhibition of human recombinant cytochrome P450s by curcumin and curcumin decomposition products. Toxicology 6-3-2007;235(1-2):83-91. PubMed
- Hou, X. L., Takahashi, K., Kinoshita, N., Qiu, F., Tanaka, K., Komatsu, K., Takahashi, K., and Azuma, J. Possible inhibitory mechanism of Curcuma drugs on CYP3A4 in 1alpha,25 dihydroxyvitamin D3 treated Caco-2 cells. Int.J Pharm 6-7-2007;337(1-2):169-177.
- Valentine, S. P., Le Nedelec, M. J., Menzies, A. R., Scandlyn, M. J., Goodin, M. G., and Rosengren, R. J. Curcumin modulates drug metabolizing enzymes in the female Swiss Webster mouse. Life Sci. 4-11-2006;78(20):2391-2398. PubMed
- Price, R. J., Scott, M. P., Giddings, A. M., Walters, D. G., Stierum, R. H., Meredith, C., and Lake, B. G. Effect of butylated hydroxytoluene, curcumin, propyl gallate and thiabendazole on cytochrome P450 forms in cultured human hepatocytes. Xenobiotica 2 PubMed
- Ganta, S., Devalapally, H., and Amiji, M. Curcumin enhances oral bioavailability and anti-tumor therapeutic efficacy of paclitaxel upon administration in nanoemulsion formulation. J Pharm Sci 2010;99(11):4630-4641. PubMed
- Lamb, S. R. and Wilkinson, S. M. Contact allergy to tetrahydrocurcumin. Contact Dermatitis 2003;48(4):227. PubMed
- Joshi, J., Ghaisas, S., Vaidya, A., Vaidya, R., Kamat, D. V., Bhagwat, A. N., and Bhide, S. Early human safety study of turmeric oil (Curcuma longa oil) administered orally in healthy volunteers. J Assoc.Physicians India 2003;51:1055-1060.
- Mahesh, T., Balasubashini, M. S., and Menon, V. P. Effect of photo-irradiated curcumin treatment against oxidative stress in streptozotocin-induced diabetic rats. J Med.Food 2005;8(2):251-255. PubMed
- Thompson, D. A. and Tan, B. B. Tetrahydracurcumin-related allergic contact dermatitis. Contact Dermatitis 2006;55(4):254-255. PubMed
- Patumraj, S., Wongeakin, N., Sridulyakul, P., Jariyapongskul, A., Futrakul, N., and Bunnag, S. Combined effects of curcumin and vitamin C to protect endothelial dysfunction in the iris tissue of STZ-induced diabetic rats. Clin Hemorheol.Microcirc. 2006;3
- Liddle, M., Hull, C., Liu, C., and Powell, D. Contact urticaria from curcumin. Dermatitis 2006;17(4):196-197. PubMed
- Juan, H., Terhaag, B., Cong, Z., Bi-Kui, Z., Rong-Hua, Z., Feng, W., Fen-Li, S., Juan, S., Jing, T., and Wen-Xing, P. Unexpected effect of concomitantly administered curcumin on the pharmacokinetics of talinolol in healthy Chinese volunteers. Eur.J Clin PubMed
- Murugan, P. and Pari, L. Influence of tetrahydrocurcumin on erythrocyte membrane bound enzymes and antioxidant status in experimental type 2 diabetic rats. J Ethnopharmacol. 9-25-2007;113(3):479-486. PubMed
- Seo, K. I., Choi, M. S., Jung, U. J., Kim, H. J., Yeo, J., Jeon, S. M., and Lee, M. K. Effect of curcumin supplementation on blood glucose, plasma insulin, and glucose homeostasis related enzyme activities in diabetic db/db mice. Mol.Nutr.Food Res 2008;5
- Weisberg, S. P., Leibel, R., and Tortoriello, D. V. Dietary curcumin significantly improves obesity-associated inflammation and diabetes in mouse models of diabesity. Endocrinology 2008;149(7):3549-3558. PubMed
- Jain, S. K., Rains, J., Croad, J., Larson, B., and Jones, K. Curcumin supplementation lowers TNF-alpha, IL-6, IL-8, and MCP-1 secretion in high glucose-treated cultured monocytes and blood levels of TNF-alpha, IL-6, MCP-1, glucose, and glycosylated hemog
- Yu, Y., Hu, S. K., and Yan, H. [The study of insulin resistance and leptin resistance on the model of simplicity obesity rats by curcumin]. Zhonghua Yu Fang Yi.Xue.Za Zhi. 2008;42(11):818-822.
- Pavithra, B. H., Prakash, N., and Jayakumar, K. Modification of pharmacokinetics of norfloxacin following oral administration of curcumin in rabbits. J Vet.Sci. 2009;10(4):293-297. PubMed
- Yan, Y. D., Kim, D. H., Sung, J. H., Yong, C. S., and Choi, H. G. Enhanced oral bioavailability of docetaxel in rats by four consecutive days of pre-treatment with curcumin. Int J Pharm 10-31-2010;399(1-2):116-120. PubMed
- Epelbaum, R., Schaffer, M., Vizel, B., Badmaev, V., and Bar-Sela, G. Curcumin and gemcitabine in patients with advanced pancreatic cancer. Nutr Cancer 2010;62(8):1137-1141. PubMed
- Madkor, H. R., Mansour, S. W., and Ramadan, G. Modulatory effects of garlic, ginger, turmeric and their mixture on hyperglycaemia, dyslipidaemia and oxidative stress in streptozotocin-nicotinamide diabetic rats. Br J Nutr 2011;105(8):1210-1217. PubMed
- Pungcharoenkul, K. and Thongnopnua, P. Effect of different curcuminoid supplement dosages on total in vivo antioxidant capacity and cholesterol levels of healthy human subjects. Phytother Res 2011;25(11):1721-1726.
- Kusuhara, H., Furuie, H., Inano, A., Sunagawa, A., Yamada, S., Wu, C., Fukizawa, S., Morimoto, N., Ieiri, I., Morishita, M., Sumita, K., Mayahara, H., Fujita, T., Maeda, K., and Sugiyama, Y. Pharmacokinetic interaction study of sulphasalazine in healthy
- Mohammadi, A., Sahebkar, A., Iranshahi, M., Amini, M., Khojasteh, R., Ghayour-Mobarhan, M., and Ferns, G. A. Effects of supplementation with curcuminoids on dyslipidemia in obese patients: a randomized crossover trial. Phytother Res 2013;27(3):374-379. PubMed
- Chuengsamarn, S., Rattanamongkolgul, S., Luechapudiporn, R., Phisalaphong, C., and Jirawatnotai, S. Curcumin extract for prevention of type 2 diabetes. Diabetes Care 2012;35(11):2121-2127. PubMed
- Goh, C. L. and Ng, S. K. Allergic contact dermatitis to Curcuma longa (turmeric). Contact Dermatitis 1987;17(3):186. PubMed
- Srivastava, R., Puri, V., Srimal, R. C., and Dhawan, B. N. Effect of curcumin on platelet aggregation and vascular prostacyclin synthesis. Arzneimittelforschung. 1986;36(4):715-717.
- Srinivasan, M. Effect of curcumin on blood sugar as seen in a diabetic subject. Indian J Med Sci 1972;26(4):269-270.
- Srivastava, K. C., Bordia, A., and Verma, S. K. Curcumin, a major component of food spice turmeric (Curcuma longa) inhibits aggregation and alters eicosanoid metabolism in human blood platelets. Prostaglandins Leukot.Essent.Fatty Acids 1995;52(4):223-227 PubMed
- Oetari, S., Sudibyo, M., Commandeur, J. N., Samhoedi, R., and Vermeulen, N. P. Effects of curcumin on cytochrome P450 and glutathione S-transferase activities in rat liver. Biochem Pharmacol 1-12-1996;51(1):39-45. PubMed
- Kiec-Swierczynska, M. and Krecisz, B. Occupational allergic contact dermatitis due to curcumin food colour in a pasta factory worker. Contact Dermatitis 1998;39(1):30-31. PubMed
- Van Dau N, Ngoc Ham N, Huy Khac D, and et al. The effects of a traditional drug, tumeric (Curcuma longa), and placebo on the healing of duodenal ulcer. Phytomed 1998;5(1):29-34.
- Daveluy A, Géniaux H, Thibaud L, Mallaret M, Miremont-Salamé G, Haramburu F. Probable interaction between an oral vitamin K antagonist and turmeric (Curcuma longa). Therapie. 2014 Nov-Dec;69(6):519-20. PubMed
- Kuptniratsaikul V, Dajpratham P, Taechaarpornkul W, Buntragulpoontawee M, Lukkanapichonchut P, Chootip C, Saengsuwan J, Tantayakom K, Laongpech S. Efficacy and safety of Curcuma domestica extracts compared with ibuprofen in patients with knee osteoarthrit
- Madhu K, Chanda K, Saji MJ. Safety and efficacy of Curcuma longa extract in the treatment of painful knee osteoarthritis: a randomized placebo-controlled trial. Inflammopharmacology 2013;21(2):129-36. PubMed
- Mali AM, Behal R, Gilda SS. Comparative evaluation of 0.1% turmeric mouthwash with 0.2% chlorhexidine gluconate in prevention of plaque and gingivitis: A clinical and microbiological study. J Indian Soc Periodontol 2012;16(3):386-91. PubMed
- Sanmukhani J, Satodia V, Trivedi J, Patel T, Tiwari D, Panchal B, Goel A, Tripathi CB. Efficacy and safety of curcumin in major depressive disorder: a randomized controlled trial. Phytother Res 2014;28(4):579-85. PubMed
- Nayeri A, Wu S, Adams E, et al. Acute Calcineurin Inhibitor Nephrotoxicity Secondary to Turmeric Intake: A Case Report. Transplant Proc. 2017;49(1):198-200. PubMed
- Mitchell TM. Correspondence re: Somasundaram et al., Dietary curcumin inhibits chemotherapy-induced apoptosis in models of human breast cancer. Cancer Res. 2003;63(16):5165-6; author reply 5166-7.
- Somasundaram S, Edmund NA, Moore DT, Small GW, Shi YY, Orlowski RZ. Dietary curcumin inhibits chemotherapy-induced apoptosis in models of human breast cancer. Cancer Res. 2002;62(13):3868-75.
- Haroyan A, Mukuchyan V, Mkrtchyan N, et al. Efficacy and safety of curcumin and its combination with boswellic acid in osteoarthritis: a comparative, randomized, double-blind, placebo-controlled study. BMC Complement Altern Med. 2018;18(1):7. PubMed
- Al-Karawi D, Al Mamoori DA, Tayyar Y. The role of curcumin administration in patients with major depressive disorder: Mini meta-analysis of clinical trials. Phytother Res. 2016;30(2):175-83. PubMed
- Neerati P, Devde R, Gangi AK. Evaluation of the effect of curcumin capsules on glyburide therapy in patients with type-2 diabetes mellitus. Phytother Res. 2014;28(12):1796-800. PubMed
- Simental-Mendía LE, Pirro M, Gotto AM Jr, et al. Lipid-modifying activity of curcuminoids: A systematic review and meta-analysis of randomized controlled trials. Crit Rev Food Sci Nutr. 2017:1-10. PubMed
- Fung FY, Wong WH, Ang SK, et al. A randomized, double-blind, placebo- controlled study on the anti-haemostatic effects of Curcuma longa, Angelica sinensis and Panax ginseng. Phytomedicine. 2017;32:88-96. PubMed
- Small GW, Siddarth P, Li Z, et al. Memory and brain amyloid and tau effects of a bioavailable form of curcumin in non-demented adults: A double-blind, placebo-controlled 18-month trial. Am J Geriatr Psychiatry. 2018;26(3):266-277.
- Cruz-Correa M, Hylind LM, Marrero JH, et al. Efficacy and safety of curcumin in treatment of intestinal adenomas in patients with familial adenomatous polyposis. Gastroenterology. 2018 May 23. Pii:S0016-5085(18)34564-5. [Epub ahead of print] PubMed
- Rahmani S, Asgary S, Askari G, et al. Treatment of non-alcoholic fatty liver disease with curcumin: a randomized placebo-controlled trial. Phytother Res. 2016 Sep;30(9):1540-8. PubMed
- Lopez-Villafuerte L, CLores KH. Contact dermatitis caused by turmeric in a massage oil. Contact Dermatitis. 2016 Jul;75(1):52-3. PubMed
- Lukefahr AL, McEvoy S, Alfafara C, Funk JL. Drug-induced autoimmune hepatitis associated with turmeric dietary supplement use. BMJ Case Rep. 2018. pii: bcr-2018-224611. PubMed
- Medsafe Safety Communication- Turmeric/Curcumin Interaction with Warfarin. April 30, 2018. Accessed at: https://medsafe.govt.nz/safety/EWS/2018/Turmeric.asp.
- Imam Z, Khasawneh M, Jomaa D, Iftikhar H, Sayedahmad Z. Drug induced liver injury attributed to a curcumin supplement. Case Rep Gastrointest Med 2019 Oct 20;2019:6029403. doi: 10.1155/2019/6029403. PubMed
- Chand S, Hair C, Beswick L. A rare case of turmeric-induced hepatotoxicity. Intern Med J. 2020;50(2):258-259. PubMed
- Jiang N, Zhang M, Meng X, Sun B. Effects of Curcumin on the Pharmacokinetics of Amlodipine in Rats and Its Potential Mechanism. Pharm Biol. 2020;58(1):465-468. PubMed
- Lee BS, Bhatia T, Chaya CT, Wen R, Taira MT, Lim BS. Autoimmune Hepatitis Associated With Turmeric Consumption. ACG Case Rep J. 2020;7(3):e00320. PubMed
- Lombardi N, Crescioli G, Maggini V, et al. Acute liver injury following turmeric use in Tuscany: an analysis of the Italian Phytovigilance database and systematic review of case reports. Br J Clin Pharmacol. 2020. PubMed
- Suhail FK, Masood U, Sharma A, John S, Dhamoon A. Turmeric supplement induced hepatotoxicity: a rare complication of a poorly regulated substance. Clin Toxicol (Phila). 2020;58(3):216-217. PubMed
- Nakagawa Y, Mukai S, Yamada S, et al. The efficacy and safety of highly-bioavailable curcumin for treating knee osteoarthritis: a 6-month open-labeled prospective study. Clin Med Insights Arthritis Musculoskelet Disord. 2020;13:1179544120948471. PubMed
- Shafabakhsh R, Asemi Z, Reiner Z, Soleimani A, Aghadavod E, Bahmani F. The effects of nano-curcumin on metabolic status in patients with diabetes on hemodialysis, a randomized, double blind, placebo-controlled trial. Iran J Kidney Dis. 2020;14(4):290-9.
- Allegri P, Rosa R, Masala A, et al. Clinical effectiveness of a new oral curcumin formulation in acute non-infectious uveitic macular edema: a 12-month observational study. Eur Rev Med Pharmacol Sci 2022;26(1):46-53.
- Tsai IC, Hsu CW, Chang CH, Tseng PT, Chang KV. The effect of curcumin differs on individual cognitive domains across different patient populations: A systematic review and meta-analysis. Pharmaceuticals (Basel) 2021;14(12):1235. PubMed
- Alam MA, Bin Jardan YA, Raish M, Al-Mohizea AM, Ahad A, Al-Jenoobi FI. Herb-drug interaction: Pharmacokinetics and pharmacodynamics of anti-hypertensive drug amlodipine besylate in presence of lepidium sativum and curcuma longa. Xenobiotica 2022;1-9.
- Sohal A, Alhankawi D, Sandhu S, Chintanaboina J. Turmeric-induced hepatotoxicity: Report of 2 cases. Int Med Case Rep J 2021;14:849-852. PubMed
- Hussaarts KGAM, Hurkmans DP, Oomen-de Hoop E, et al. Impact of curcumin (with or without piperine) on the pharmacokinetics of tamoxifen. Cancers (Basel). 2019;11(3):403. PubMed
- Kalluru H, Mallayasamy SR, Kondaveeti SS, Chandrasekhar V, Kalachaveedu M. Effect of turmeric supplementation on the pharmacokinetics of paclitaxel in breast cancer patients: A study with population pharmacokinetics approach. Phytother Res 2022;36(4):1761 PubMed
- 109288 Halegoua-DeMarzio D, Navarro V, Ahmad J, et al. Liver injury associated with turmeric-A growing problem: Ten cases from the drug-induced liver injury network [DILIN]. Am J Med. 2022:S0002-9343(22)00740-9. PubMed
- Arzallus T, Izagirre A, Castiella A, Torrente S, Garmendia M, Zapata EM. Drug induced autoimmune hepatitis after turmeric intake. Gastroenterol Hepatol 2023. PubMed
- Gilad O, Rosner G, Ivancovsky-Wajcman D, et al. Efficacy of wholistic turmeric supplement on adenomatous polyps in patients with familial adenomatous polyposis-A randomized, double-blinded, placebo-controlled study. Genes (Basel) 2022;13(12):2182. PubMed
- Ahad A, Raish M, Abdelrahman IA, et al. Changes in pharmacokinetics and pharmacodynamics of losartan in experimental diseased rats treated with Curcuma longa and Lepidium sativum. Pharmaceuticals (Basel) 2022;16(1):33. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
- Kou H, Huang L, Jin M, He Q, Zhang R, Ma J. Effect of curcumin on rheumatoid arthritis: a systematic review and meta-analysis. Front Immunol 2023;14:1121655. PubMed
- Qiu L, Gao C, Wang H, et al. Effects of dietary polyphenol curcumin supplementation on metabolic, inflammatory, and oxidative stress indices in patients with metabolic syndrome: a systematic review and meta-analysis of randomized controlled trials. Front PubMed
- Sato T, Yagi A, Yamauchi M, et al. The use of an antioxidant enables accurate evaluation of the interaction of curcumin on organic anion-transporting polypeptides 4C1 by preventing auto-oxidation. Int J Mol Sci 2024;25(2):991. PubMed
- Washington O, Robinson E, Simh D, et al. Oxalate nephropathy and chronic turmeric supplementation: a case report. J Bras Nefrol 2024;46(1):99-106. PubMed
- Munshi R, Karande-Patil S, Kumbhar D, Deshmukh A, Hingorani L. A randomized, controlled, comparative, proof-of-concept study to evaluate the efficacy and safety of Nisha-Amalaki capsules in prediabetic patients for preventing progression to diabetes. J Ay PubMed
- Sharifi Razavi A, Mohajerani F, Niksolat F, Karimi N. Efficacy of topical curcumin on mild to moderate carpal tunnel syndrome: a randomized double-blind, placebo-controlled clinical trial. Pain Med 2024;25(5):327-333. PubMed
- Yaikwawong M, Jansarikit L, Jirawatnotai S, Chuengsamarn S. Curcumin Reduces Depression in Obese Patients with Type 2 Diabetes: A Randomized Controlled Trial. Nutrients 2024;16(15):2414. PubMed
- Tehrani SD, Hosseini A, Shahzamani M, et al. Evaluation of the effectiveness of curcumin and piperine co-supplementation on inflammatory factors, cardiac biomarkers, atrial fibrillation, and clinical outcomes after coronary artery bypass graft surgery. Cl PubMed
- Yaikwawong M, Jansarikit L, Jirawatnotai S, Chuengsamarn S. The Effect of Curcumin on Reducing Atherogenic Risks in Obese Patients with Type 2 Diabetes: A Randomized Controlled Trial. Nutrients 2024;16(15):2441. PubMed
- Dibaei M, Hosseini A, Lavasani H, Kiani-Dehkordi B, Rouini M. Assessment of metabolic interaction between curcumin and tramadol using the isolated perfused rat liver. Heliyon 2024;10(15):e35070. PubMed
Calcium 62 references
- Shils M, Olson A, Shike M. Modern Nutrition in Health and Disease. 8th ed. Philadelphia, PA: Lea and Febiger, 1994.
- Hernandez-Avila M, Gonzalez-Cossio T, Hernandez-Avila JE, et al. Dietary calcium supplements to lower blood lead levels in lactating women: a randomized placebo-controlled trial. Epidemiology 2003;14:206-12.. PubMed
- Thys-Jacobs S, Ceccarelli S, Bierman A, et al. Calcium supplementation in premenstrual syndrome: a randomized crossover trial. J Gen Intern Med 1989;4:183-9. PubMed
- Maton PN, Burton ME. Antacids revisited: a review of their clinical pharmacology and recommended therapeutic use. Drugs 1999;57:855-70.
- Clemens JD, Feinstein AR. Calcium carbonate and constipation: a historical review of medical mythopoeia. Gastroenterology 1977;72:957-61. DOI
- Saunders D, Sillery J, Chapman R. Effect of calcium carbonate and aluminum hydroxide on human intestinal function. Dig Dis Sci 1988;33:409-13. PubMed
- Friedman PA, Bushinsky DA. Diuretic effects on calcium metabolism. Semin Nephrol 1999;19:551-6.
- Koo WK, Walters JC, Esterlitz J, et al. Maternal calcium supplementation and fetal bone mineralization. Obstet Gynecol 1999;94:577-82. DOI
- Raman L, Rajalakshmi K, Krishnamachari KAVR, et al. Effect of calcium supplementation to undernourished mothers during pregnancy on the bone density of the neonates. Am J Clin Nutr 1978; 31:466-9. DOI
- Murry JJ, Healy MD. Drug-mineral interactions: a new responsibility for the hospital dietician. J Am Diet Assoc 1991;91:66-73.
- Chan JM, Giovannucci E, Andersson SO, et al. Dairy products, calcium, phosphorous, vitamin D, and risk of prostate cancer. Cancer Causes Control 1998;9:559-66.
- Butner LE, Fulco PP, Feldman G, et al. Calcium carbonate-induced hypothyroidism. Ann Intern Med 2000:132:595. PubMed
- Schneyer CR. Calcium carbonate and reduction of levothyroxine efficacy. JAMA 1998;279:750. PubMed
- Moser LR, Smythe MA, Tisdale JE. The use of calcium salts in the prevention and management of verapamil-induced hypotension. Ann Pharmacother 2000;34:622-9. PubMed
- Singh N, Singh PN, Hershman JM. Effect of calcium carbonate on the absorption of levothyroxine. JAMA 2000;283:2822-5. PubMed
- Kahela P, Anttila M, Tikkanen R, Sundquist H. Effect of food, food constituents and fluid volume on the bioavailability of sotalol. Acta Pharmacol Toxicol (Copenh) 1979;44:7-12.. PubMed
- Pletz MW, Petzold P, Allen A, et al. Effect of calcium carbonate on bioavailability of orally administered gemifloxacin. Antimicrob Agents Chemother 2003;47:2158-60.. PubMed
- Bar-Or D, Yoel G. Calcium and calciferol antagonize effect of verapamil in atrial fibrillation. Br Med J 1981;282:1585-6.
- Decktor DL, Robinson M, Maton PN, et al. Effects of aluminum/magnesium hydroxide and calcium carbonate on esophageal and gastric pH in subjects with heartburn. Am J Ther 1995;2:546-52. PubMed
- Simoneau G. Absence of rebound effect with calcium carbonate. Eur J Drug Metab Pharmacokinet 1996;21:351-7. PubMed
- Peters ML, Leonard M, Licata AA. Role of alendronate and risedronate in preventing and treating osteoporosis. Cleve Clin J Med 2001;68:945-51. PubMed
- Bourke JF, Mumford R, Whittaker P, et al. The effects of topical calcipotriol on systemic calcium homeostasis in patients with chronic plaque psoriasis. J Am Acad Dermatol 1997;37:929-34.
- Gueguen L, Pointillart A. The bioavailability of dietary calcium. J Am Coll Nutr 2000;19:119s-136s. PubMed
- Vella A, Gerber TC, Hayes DL, Reeder GS. Digoxin, hypercalcaemia, and cardiac conduction. Postgrad Med J 1999;75:554-6. PubMed
- Bania TC, Blaufeux B, Hughes S, et al. Calcium and digoxin vs. calcium alone for severe verapamil toxicity. Acad Emerg Med 2000;7:1089-96. PubMed
- Tseng M, Breslow RA, Graubard BI, Ziegler RG. Dairy, calcium, and vitamin D intakes and prostate cancer risk in the National Health and Nutrition Examination Epidemiologic Follow-up Study cohort. Am J Clin Nutr 2005;81:1147-54. PubMed
- Weingarten MA, Zalmanovici A, Yaphe J. Dietary calcium supplementation for preventing colorectal cancer and adenomatous polyps. Cochrane Database Syst Rev 2004;(1):CD003548. PubMed
- Tavani A, Bertuccio P, Bosetti C, et al. Dietary intake of calcium, vitamin D, phosphorus and the risk of prostate cancer. Eur Urol 2005;48:27-33. PubMed
- Giovannucci E, Liu Y, Stampfer MJ, Willett WC. A prospective study of calcium intake and incident and fatal prostate cancer. Cancer Epidemiol Biomarkers Prev 2006;15:203-10. PubMed
- Rocephin (ceftriaxone) and calcium interaction. Pharmacist's Letter / Prescriber's Letter 2007;23(10):231005.
- Bolland MJ, Barber PA, Doughty RN, et al. Vascular events in healthy older women receiving calcium supplementation: randomised control trial. BMJ 2008;336:262-6.
- Bolland MJ, Avenell A, Baron JA, et al. Effect of calcium supplements on risk of myocardial infarction and cardiovascular events: meta-analysis. BMJ 2010;341:c3691. PubMed
- Calcium supplementation and vascular events. Pharmacist's Letter / Prescriber's Letter 2008;24(3):240306.
- Dietary reference intakes for calcium and vitamin D. Institute of Medicine, November 30, 2010. Available at: http://www.iom.edu/~/media/Files/Report%20Files/2010/Dietary-Reference-Intakes-for-Calcium-and-Vitamin-D/Vitamin%20D%20and%20Calcium%202010%20Repo
- Coburn JW, Mischel MG, Goodman WG, et al. Calcium citrate markedly enhances aluminum absorption from aluminum hydroxide. Am J Kidney Dis. 1991;17(6):708-11. PubMed
- Bradley JS, Wassel RT, Lee L, et al. Intravenous ceftriaxone and calcium in the neonate: assessing the risk for cardiopulmonary adverse events. Pediatrics. 2009;123(4):e609-13. PubMed
- Kays MB, Overholser BR, Mueller BA, et al. Effects of sevelamer hydrochloride and calcium acetate on the oral bioavailability of ciprofloxacin. Am J Kidney Dis. 2003;42(6):1253-9. PubMed
- Neuhofel, A. L., Wilton, J. H., Victory, J. M., Hejmanowsk, L. G., and Amsden, G. W. Lack of bioequivalence of ciprofloxacin when administered with calcium-fortified orange juice: a new twist on an old interaction. J Clin Pharmacol. 2002;42(4):461-466. DOI
- Dickinson, H. O., Nicolson, D. J., Cook, J. V., Campbell, F., Beyer, F. R., Ford, G. A., and Mason, J. Calcium supplementation for the management of primary hypertension in adults. Cochrane.Database.Syst.Rev. 2006;(2):CD004639. PubMed
- Jones, B. J. and Twomey, P. J. Requesting patterns for serum calcium concentration in patients on long-term lithium therapy. Int J Clin Pract. 2009;63(1):170-172. PubMed
- Levine, M., Nikkanen, H., and Pallin, D. J. The effects of intravenous calcium in patients with digoxin toxicity. J Emerg.Med. 2011;40(1):41-46. PubMed
- Castelo-Branco, C., Ciria-Recasens, M., Cancelo-Hidalgo, M. J., Palacios, S., Haya-Palazuelos, J., Carbonell-Abello, J., Blanch-Rubio, J., Martinez-Zapata, M. J., Manasanch, J., and Perez-Edo, L. Efficacy of ossein-hydroxyapatite complex compared with ca
- Li K, Kaaks R, Linseisen J, Rohrmann S. Associations of dietary calcium intake and calcium supplementation with myocardial infarction and stroke risk and overall cardiovascular mortality in the Heidelberg cohort of the European Prospective Investigation i
- Chung M, Tang AM, Fu Z. Calcium Intake and Cardiovascular Disease Risk: An Updated Systematic Review and Meta-analysis. Ann Intern Med. 2016 Oct 25. PubMed
- Nolan CR, Califano JR, Butzin CA. Influence of calcium acetate or calcium citrate on intestinal aluminum absorption. Kidney Int. 1990;38(5):937-41. PubMed
- Lewis JR, Radavelli-Bagatini S, Rejnmark L, et al. The effects of calcium supplementation on verified coronary heart disease hospitalization and death in postmenopausal women: a collaborative meta-analysis of randomized controlled trials. J Bone Miner Res PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Lappe J, Watson P, Travers-Gustafson D, Recker R, Garland C, Gorham E, Baggerly K, McDonnell SL. Effect of Vitamin D and Calcium Supplementation on Cancer Incidence in Older Women: A Randomized Clinical Trial. JAMA. 2017 Mar 28;317(12):1234-1243. PubMed
- Grove ML, Cook D. Calcium and heart attacks. Doesn't apply to most calcium prescriptions. BMJ. 2010;341:c5003. PubMed
- Insentress [package insert]. Whitehouse Station, NJ: Merck Sharp & Dohme Corp.; 2014.
- Roberts JL, Kiser JJ, Hindman JT, Meditz AL. Virologic failure with a raltegravir-containing antiretroviral regimen and concomitant calcium administration. Pharmacotherapy 2011;31(10):298e-302e. DOI
- Vitekta [package insert]. Foster City, CA: Gilead Sciences, Inc.; 2014.
- Storan ER, O'Gorman SM, Murphy A, Laing M. Case Report of Calciphylaxis Secondary to Calcium and Vitamin D<sub>3</sub> Supplementation. J Cutan Med Surg. 2017;21(2):162-163. DOI
- Jenkins DJA, Spence JD, Giovannucci EL, et al. Supplemental vitamins and minerals for CVD prevention and treatment. J Am Coll Cardiol 2018;71(22):2570-84. PubMed
- Borkenhagen JF, Connor EL, Stafstrom CE. Neonatal hypocalcemic seizures due to excessive maternal calcium ingestion. Pediatr Neurol 2013;48(6):469-71. PubMed
- WHO recommendations on antenatal care for a positive pregnancy experience. Geneva: World Health Organization; 2016 (http://www.who.int/reproductivehealth/publications/maternal_perinatal_health/ anc-positive-pregnancy-experience/en/).
- Aune D, Navarro Rosenblatt DA, Chan DS, et al. Dairy products, calcium, and prostate cancer risk: a systematic review and meta-analysis of cohort studies. Am J Clin Nutr. 2015;101(1):87-117. PubMed
- Lan T, Park Y, Colditz GA, et al. Adolescent dairy product and calcium intake in relation to later prostate cancer risk and mortality in the NIH-AARP Diet and Health Study. Cancer Causes Control. 2020;31(10):891-904. PubMed
- Zhang Y, Li Y, Liu J, et al. Association of Vitamin D or Calcium Supplementation with Cardiovascular Outcomes and Mortality: A Meta-Analysis with Trial Sequential Analysis. J Nutr Health Aging 2021;25(2):263-270. PubMed
- Myung SK, Kim HB, Lee YJ, Choi YJ, Oh SW. Calcium Supplements and Risk of Cardiovascular Disease: A Meta-Analysis of Clinical Trials. Nutrients 2021;13(2):368. PubMed
- Hetaimish B. Neonatal Calcinosis Cutis After Treatment of Hypocalcemia with Calcium Gluconate: A Report of 2 Cases. Am J Case Rep 2024;25:e943397. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Milk Thistle 69 references
- Ferenci P, Dragosics B, Dittrich H, et al. Randomized controlled trial of silymarin treatment in patients with cirrhosis of the liver. J Hepatol 1989;9:105-13. PubMed
- Anon. Milk thistle: Effects on liver disease and cirrhosis and clinical adverse effects. Summary, Evidence Report/Technology Assessment: Number 21, September 2000. Agency for Healthcare Research and Quality, Rockville, MD. Available at: http://www.ahrq.g
- Beckmann-Knopp S, Rietbrock S, Weyhenmeyer R, et al. Inhibitory effects of silibinin on cytochrome P-450 enzymes in human liver microsomes. Pharmacol Toxicol 2000;86:250-6. PubMed
- Venkataramanan R, Ramachandran V, Komoroski BJ, et al. Milk thistle, a herbal supplement, decreases the activity of CYP3A4 and uridine diphosphoglucuronosyl transferase in human hepatocyte cultures. Drug Metab Dispos 2000;28:1270-3. DOI
- Kim DH, Jin YH, Park JB, Kobashi K. Silymarin and its components are inhibitors of beta-glucuronidase. Biol Pharm Bull 1994;17:443-5. PubMed
- Pares A, Planas R, Torres M, et al. Effects of silymarin in alcoholic patients with cirrhosis of the liver: results of a controlled, double-blind, randomized and multicenter trial. J Hepatol 1998;28:615-21. PubMed
- Piscitelli SC, Formentini E, Burstein AH, et al. Effect of milk thistle on the pharmacokinetics of indinavir in healthy volunteers. Pharmacotherapy 2002;22:551-6. PubMed
- Boerth J, Strong KM. The clinical utility of milk thistle (Silybum marianum) in cirrhosis of the liver. J Herb Pharmacother 2002;2:11-7.
- Tanamly MD, Tadros F, Labeeb S, et al. Randomised double-blinded trial evaluating silymarin for chronic hepatitis C in an Egyptian village: study description and 12-month results. Dig Liver Dis 2004;36:752-9. PubMed
- Gurley BJ, Gardner SF, Hubbard MA, et al. In vivo assessment of botanical supplementation on human cytochrome P450 phenotypes: Citrus aurantium, Echinacea purpurea, milk thistle, and saw palmetto. Clin Pharmacol Ther 2004;76:428-40. .
- Huseini HF, Larijani B, Heshmat R, et al. The efficacy of Silybum marianum (L.) Gaertn. (silymarin) in the treatment of type II diabetes: a randomized, double-blind, placebo-controlled, clinical trial. Phytother Res 2006;20;1036-9.
- Deng JW, Shon JH, Shin HJ, et al. Effect of silymarin supplement on the pharmacokinetics of rosuvastatin. Pharm Res 2008;25:1807-14. PubMed
- Kim CS, Choi SJ, Park CY, et al. Effects of silybinin on the pharmacokinetics of tamoxifen and its active metabolite, 4-hydroxytamoxifen in rats. Anticancer Res 2010;30:79-85.
- Sridar C, Goosen TC, Kent UM, et al. Silybin inactivates cytochromes P450 3A4 and 2C9 and inhibits major hepatic glucuronosyltransferases. Drug Metab Dispos 2004;32:587-94. PubMed
- van Erp NP, Baker SD, Zhao M, et al. Effect of milk thistle (Silybum marianum) on the pharmacokinetics of irinotecan. Clin Cancer Res 2005;11:7800-6.
- Budzinski JW, Trudeau VL, Drouin CE, et al. Modulation of human cytochrome P450 3A4 (CYP3A4) and P-glycoprotein (P-gp) in Caco-2 cell monolayers by selected commercial-source milk thistle and goldenseal products. Can J Physiol Pharmacol 2007;85:966-78.
- Doehmer J, Weiss G, McGregor GP, Appel K. Assessment of a dry extract from milk thistle (Silybum marianum) for interference with human liver cytochrome-P450 activities. Toxicol In Vitro 2011;25:21-7. PubMed
- Jiao Z, Shi XJ, Li ZD, et al. Population pharmacokinetics of sirolimus in de novo Chinese adult renal transplant patients. Br.J.Clin.Pharmacol. 2009;68(1):47-60.
- Gurley, B. J., Barone, G. W., Williams, D. K., Carrier, J., Breen, P., Yates, C. R., Song, P. F., Hubbard, M. A., Tong, Y., and Cheboyina, S. Effect of milk thistle (Silybum marianum) and black cohosh (Cimicifuga racemosa) supplementation on digoxin phar
- Allain, H., Schuck, S., Lebreton, S., Strenge-Hesse, A., Braun, W., Gandon, J. M., and Brissot, P. Aminotransferase levels and silymarin in de novo tacrine-treated patients with Alzheimer's disease. Dement.Geriatr.Cogn Disord. 1999;10(3):181-185. PubMed
- Angulo, P., Patel, T., Jorgensen, R. A., Therneau, T. M., and Lindor, K. D. Silymarin in the treatment of patients with primary biliary cirrhosis with a suboptimal response to ursodeoxycholic acid. Hepatology 2000;32(5):897-900. PubMed
- Bean, P. The use of alternative medicine in the treatment of hepatitis C. Am.Clin.Lab 2002;21(4):19-21.
- Hussain, S. A. Silymarin as an adjunct to glibenclamide therapy improves long-term and postprandial glycemic control and body mass index in type 2 diabetes. J.Med.Food 2007;10(3):543-547. PubMed
- El-Kamary, S. S., Shardell, M. D., Abdel-Hamid, M., Ismail, S., El-Ateek, M., Metwally, M., Mikhail, N., Hashem, M., Mousa, A., Aboul-Fotouh, A., El-Kassas, M., Esmat, G., and Strickland, G. T. A randomized controlled trial to assess the safety and effic
- Gharagozloo, M., Moayedi, B., Zakerinia, M., Hamidi, M., Karimi, M., Maracy, M., and Amirghofran, Z. Combined therapy of silymarin and desferrioxamine in patients with beta-thalassemia major: a randomized double-blind clinical trial. Fundam.Clin.Pharmaco
- Ladas, E. J., Kroll, D. J., Oberlies, N. H., Cheng, B., Ndao, D. H., Rheingold, S. R., and Kelly, K. M. A randomized, controlled, double-blind, pilot study of milk thistle for the treatment of hepatotoxicity in childhood acute lymphoblastic leukemia (ALL PubMed
- Sayyah, M., Boostani, H., Pakseresht, S., and Malayeri, A. Comparison of Silybum marianum (L.) Gaertn. with fluoxetine in the treatment of Obsessive-Compulsive Disorder. Prog.Neuropsychopharmacol.Biol.Psychiatry 3-17-2010;34(2):362-365. PubMed
- Flaig, T. W., Glode, M., Gustafson, D., van, Bokhoven A., Tao, Y., Wilson, S., Su, L. J., Li, Y., Harrison, G., Agarwal, R., Crawford, E. D., Lucia, M. S., and Pollak, M. A study of high-dose oral silybin-phytosome followed by prostatectomy in patients w
- Ramirez-Santos, A., Perez-Bustillo, A., Gonzalez-Sixto, B., Suarez-Amor, O., and Rodriguez-Prieto, M. A. [Acute generalized exanthematous pustulosis due to milk thistle (Silybum marianum) tea]. Actas Dermosifiliogr. 2011;102(9):744-745. DOI
- Loguercio C, Andreone P, Brisc C, et al. Silybin combined with phosphatidylcholine and vitamin E in patients with nonalcoholic fatty liver disease: a randomized controlled trial. Free Radic Biol Med 2012;52(9):1658-65. PubMed
- Yakoot, M. and Salem, A. Spirulina platensis versus silymarin in the treatment of chronic hepatitis C virus infection. A pilot randomized, comparative clinical trial. BMC.Gastroenterol. 2012;12:32. PubMed
- Fallahzadeh, M. K., Dormanesh, B., Sagheb, M. M., Roozbeh, J., Vessal, G., Pakfetrat, M., Daneshbod, Y., Kamali-Sarvestani, E., and Lankarani, K. B. Effect of addition of silymarin to renin-angiotensin system inhibitors on proteinuria in type 2 diabetic
- Fried, M. W., Navarro, V. J., Afdhal, N., Belle, S. H., Wahed, A. S., Hawke, R. L., Doo, E., Meyers, C. M., and Reddy, K. R. Effect of silymarin (milk thistle) on liver disease in patients with chronic hepatitis C unsuccessfully treated with interferon t
- Fallah Huseini, H., Larijani, B., Fakhrzadeh, H., Rajabi Pour, B., Akhondzadeh, S., Toliat, T., and Heshmat, R. The clinical trial of Silybum Marianum seed extract (Silymarin) on type II diabetic patients with hyperlipidemia. Iran J.Diabetes Lipid Disord
- Mironets VI, Krasovskaia EA, and Polishchuk II. [A case of urticaria during Carsil treatment]. Vrach Delo 1990;7:86-87.
- Velussi M, Cernigoi AM, Viezzoli L, and et al. Silymarin reduces hyperinsulinemia, malondialdehyde levels, and daily insulin need in cirrhotic diabetic patients. Curr Ther Res 1993;53(5):533-545. DOI
- Marcelli R, Bizzoni P, Conte D, and et al. Randomized controlled study of the efficacy and tolerability of a short course of IdB 1016 in the treatment of chronic persistent hepatitis. Eur Bull Drug Res 1992;1(3):131-135.
- Vailati A, Aristia L, Sozze E, and et al. Randomized open study of the dose-effect relationship of a short course of IdB 1016 in patients with viral or alcoholic hepatitis. Fitoterapia 1993;64(3):219-228.
- Marena C and Lampertico M. Preliminary clinical development of silipide: a new complex of silybin in toxic liver disorders. Planta Med 1991;57(2):A124-A125. DOI
- Grungreiff K, Albrecht M, and Strenge-Hesse A. Benefit of medicinal liver therapy in general practice. Med Welt 1995;46:222-227.
- Frerick F, Kuhn U, and Strenge-Hesse A. Silymarin--ein Phytopharmakon zur Behandlung toxischen Leberschaden: Anwendungsbeobachtung bei 2169 Patienten. Kassenarzt 1990;33:36-41.
- Schuppan D, Strosser W, Burkard G, and et al. Influence of Legalon(TM) 140 on the metabolism of collagen in patients with chronic liver disease--Review by measurement of PIIINP-values. Zeitschrift fur Allgemeinmedizin 1998;74:577-584.
- Studlar M. Die Behandlung chronischer Leberkrankungen mit Silymarin und B-Vitaminen. Therapiewoche 1985;35:3375-3378.
- Anon. Adverse reaction: milk thistle-associated toxicity. Nurse Drug Alert 1999;23(7):51.
- Gufford BT, Chen G, Vergara AG, et al. Milk Thistle Constituents Inhibit Raloxifene Intestinal Glucuronidation: A Potential Clinically Relevant Natural Product-Drug Interaction. Drug Metab Dispos. 2015;43(9):1353-9. PubMed
- El-Shitany NA, Hegazy S, El-Desoky K. Evidences for antiosteoporotic and selective estrogen receptor modulator activity of silymarin compared with ethinylestradiol in ovariectomized rats. Phytomedicine. 2010;17(2):116-25. PubMed
- Seidlová-Wuttke D, Becker T, Christoffel V, Jarry H, Wuttke W. Silymarin is a selective estrogen receptor beta (ERbeta) agonist and has estrogenic effects in the metaphysis of the femur but no or antiestrogenic effects in the uterus of ovariectomized (ovx
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Derosa G, Romano D, D'Angelo A, Maffioli P. Berberis aristata/Silybum marianum fixed combination (Berberol(®)) effects on lipid profile in dyslipidemic patients intolerant to statins at high dosages: a randomized, placebo-controlled, clinical trial. Phyto PubMed
- Luangchosiri C, Thakkinstian A, Chitphuk S, Stitchantrakul W, Petraksa S, Sobhonslidsuk A. A double-blinded randomized controlled trial of silymarin for the prevention of antituberculosis drug-induced liver injury. BMC Complement Altern Med. 2015;15:334. PubMed
- Kawaguchi-Suzuki M, Frye RF, Zhu HJ, et al. The effects of milk thistle (Silybum marianum) on human cytochrome P450 activity. Drug Metab Dispos. 2014;42(10):1611-6. PubMed
- Rastegarpanah M, Malekzadeh R, Vahedi H, et al. A randomized, double blinded, placebo-controlled clinical trial of silymarin in ulcerative colitis. Chin J Integr Med. 2015;21(12):902-6. PubMed
- Di Pierro F, Bellone I, Rapacioli G, Putignano P. Clinical role of a fixed combination of standardized Berberis aristata and Silybum marianum extracts in diabetic and hypercholesterolemic patients intolerant to statins. Diabetes Metab Syndr Obes. 2015;8:8 PubMed
- Di Pierro F, Villanova N, Agostini F, Marzocchi R, Soverini V, Marchesini G. Pilot study on the additive effects of berberine and oral type 2 diabetes agents for patients with suboptimal glycemic control. Diabetes Metab Syndr Obes. 2012;5:213-7. PubMed
- Guarino G, Strollo F, Carbone L, et al. Bioimpedance analysis, metabolic effects and safety of the association Berberis aristata/Bilybum marianum: a 52-week double-blind, placebo-controlled study in obese patients with type 2 diabetes. J Biol Regul Homeos
- Ebrahimpour-Koujan S, Gargari BP, Mobasseri M, Valizadeh H, Asghari-Jafarabadi M. Lower glycemic indices and lipid profile among type 2 diabetes mellitus patients who received novel dose of Silybum marianum (L.) Gaertn. (silymarin) extract supplement: A T
- Lash DB, Ward S. CYP2C9-mediated warfarin and milk thistle interaction. J Clin Pharm Ther. 2019. PubMed
- Malekshah RE, Khaleghian A. Influence of Silybum marianum on morphine addicted rats, biochemical parameters and molecular simulation studies on µ-opioid receptor. Drug Res (Stuttg). 2019;69(11):630-638. PubMed
- Soleymani S, Ayati MH, Mansourzadeh MJ, Namazi N, Zargaran A. The effects of Silymarin on the features of cardiometabolic syndrome in adults: A systematic review and meta-analysis. Phytother Res. 2022 Jan 11. doi: 10.1002/ptr.7364. PubMed
- Gamissans M, Expósito-Serrano V, López-Llunell C, Valdivieso L, Garbayo-Salmons P. Bullous pemphigoid triggered by Silybum marianum: an unexpected side effect of an herbal remedy. Int J Dermatol. 2021 Aug 7. doi: 10.1111/ijd.15822. PubMed
- Aboras SI, Korany MA, El-Yazbi AF, Ragab MAA, Abdine HH. In-depth investigation of the Silymarin effect on the pharmacokinetic parameters of sofosbuvir, GS-331007 and ledipasvir in rat plasma using LC-MS. Biomed Chromatogr 2022;36(9):e5427. PubMed
- Wattanakrai P, Nimmannitya K. A Randomized, Double-Blind, Split-Face Study of Topical Silymarin vs 2% Hydroquinone Cream in Melasmas. J Drugs Dermatol 2022;21(12):1304-1310. PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
- Zhang W, Zhang Y, Wen C, Jiang X, Wang L. In vitro Assessment of the Effects of Silybin on CYP2B6-mediated Metabolism. Planta Med 2023. PubMed
- Bechtold BJ, Lynch KD, Oyanna VO, et al. Rifampin- and Silymarin-Mediated Pharmacokinetic Interactions of Exogenous and Endogenous Substrates in a Transgenic OATP1B Mouse Model. Mol Pharm 2024;21(5):2284-2297. PubMed
- Mohammadi S, Asbaghi O, Afrisham R, et al. Impacts of Supplementation with Silymarin on Cardiovascular Risk Factors: A Systematic Review and Dose-Response Meta-Analysis. Antioxidants (Basel) 2024;13(4):390. PubMed
- Rustamzadeh A, Sadigh N, Vahabi Z, et al. Effects silymarin and rosuvastatin on amyloid-carriers level in dyslipidemic Alzheimer's patients: A double-blind placebo-controlled randomized clinical trial. IBRO Neurosci Rep 2024;17:108-121. PubMed
- Fatemi Shandiz A, Karimi G, Dayyani M, Hosseini S, Elyasi S. Evaluation of oral silymarin formulation efficacy in prevention of doxorubicin induced hepatotoxicity in patients with non-metastatic breast cancer. J Oncol Pharm Pract 2024. PubMed
- Duan X, Bai W, Hu J, et al. Inhibitory effect of flavonoids on multidrug and toxin extrusion protein 1 function: Implications for food/herb-drug interaction and drug-induced kidney injury. J Appl Toxicol 2024;44(9):1388-1402. PubMed
Artichoke 16 references
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- Walker AF, Middleton RW, Petrowicz O. Artichoke leaf extract reduces symptoms of irritable bowel syndrome in a post-marketing surveillance study. Phytother Res 2001;15:58-61. PubMed
- Pittler MH, White AR, Stevinson C, Ernst E. Effectiveness of artichoke extract in preventing alcohol-induced hangovers: a randomized controlled trial. CMAJ 2003;169:1269-73.
- Romano, C., Ferrara, A., and Falagiani, P. A case of allergy to globe artichoke and other clinical cases of rare food allergy. J Investig.Allergol.Clin Immunol. 2000;10(2):102-104.
- Miralles, J. C., Garcia-Sells, J., Bartolome, B., and Negro, J. M. Occupational rhinitis and bronchial asthma due to artichoke (Cynara scolymus). Ann Allergy Asthma Immunol. 2003;91(1):92-95. PubMed
- Franck, P., Moneret-Vautrin, D. A., Morisset, M., Kanny, G., Megret-Gabeaux, M. L., and Olivier, J. L. Anaphylactic reaction to inulin: first identification of specific IgEs to an inulin protein compound. Int Arch Allergy Immunol 2005;136(2):155-158. PubMed
- Meding, B. Allergic contact dermatitis from artichoke, Cynara scolymus. Contact Dermatitis 1983;9(4):314.
- Quirce, S., Tabar, A. I., Olaguibel, J. M., and Cuevas, M. Occupational contact urticaria syndrome caused by globe artichoke (Cynara scolymus). J Allergy Clin Immunol. 1996;97(2):710-711. PubMed
- Held C. Von der 1. Deutsche-Ungarischen Phytopharmakon-Konferenz, Budapest, 20. November 1991. Z Klin Med 1992;47:92-93.
- Barrat E, Zaïr Y, Ogier N, et al. A combined natural supplement lowers LDL cholesterol in subjects with moderate untreated hypercholesterolemia: a randomized placebo-controlled trial. Int J Food Sci Nutr. 2013;64(7):882-9. PubMed
- Huber R, Müller M, Naumann J, Schenk T, Lüdtke R. Artichoke leave extract for chronic hepatitis C - a pilot study. Phytomedicine. 2009 Sep;16(9):801-4. PubMed
- Caputo F, Barranco R, Bonsignore A, Fraternali Orcioni G, Ventura F. A rare case of fatal bowel obstruction secondary to a colonic bezoar. Am J Forensic Med Pathol. 2018;39(1):38-40. PubMed
- Elsebai MF, Abass K, Hakkola J, Atawia AR, Farag MA. The wild Egyptian artichoke as a promising functional food for the treatment of hepatitis C virus as revealed via UPLC-MS and clinical trials. Food Funct. 2016;7(7):3006-16. PubMed
- Moradi M, Sohrabi G, Golbidi M, et al. Effects of artichoke on blood pressure: a systematic review and meta-analysis. Complement Ther Med 2021;57:102668. PubMed
- Jalili C, Moradi S, Babaei A, et al. Effects of Cynara scolymus L. on glycemic indices: a systematic review and meta-analysis of randomized clinical trials. Complement Ther Med 2020;52:102496. PubMed
- Gallo R, Oddenino G, Trave I, Gasparini G, Guadagno A, Parodi A. Contact sensitivity to sesquiterpene lactone mix and artichoke in a patient with severe recurrent dermatitis: A puzzling case. Contact Dermatitis 2023;88(2):156-158. PubMed
Dandelion 27 references
- Maliakal PP, Wanwimolruk S. Effect of herbal teas on hepatic drug metabolizing enzymes in rats. J Pharm Pharmacol 2001;53:1323-9. PubMed
- Williams CA, Goldstone F, Greenham J. Flavonoids, cinnamic acids and coumarins from the different tissues and medicinal preparations of Taraxacum officinale. Phytochemistry 1996;42:121-7. PubMed
- Hussain Z, Waheed A, Qureshi RA, et al. The effect of medicinal plants of Islamabad and Murree region of Pakistan on insulin secretion from INS-1 cells. Phytother Res 2004;18:73-7. PubMed
- Racz-Kotilla E, Racz G, Solomon A. The action of Taraxacum officinale extracts on the body weight and diuresis of laboratory animals. Planta Med 1974;26:212-7. PubMed
- Zhu M, Wong PY, Li RC. Effects of taraxacum mongolicum on the bioavailability and disposition of ciprofloxacin in rats. J Pharm Sci 1999;88:632-4. PubMed
- Jovanovic M, Mimica-Dukic N, Poljacki M, Boza P. Erythema multiforme due to contact with weeds: a recurrence after patch testing. Contact Dermatitis 2003;48:17-25. PubMed
- Chivato T, Juan F, Montoro A, Laguna R. Anaphylaxis induced by ingestion of a pollen compound. J Investig Allergol Clin Immunol 1996;6:208-9.
- Cohen SH, Yunginger JW, Rosenberg N, Fink JN. Acute allergic reaction after composite pollen ingestion. J Allergy Clin Immunol 1979;64:270-4. PubMed
- Lovell CR, Rowan M. Dandelion dermatitis. Contact Dermatitis 1991;25:185-8. PubMed
- Agarwal SC, Crook JR, Pepper CB. Herbal remedies -- how safe are they? A case report of polymorphic ventricular tachycardia/ventricular fibrillation induced by herbal medication used for obesity. Int J Cardiol 2006;106:260-1. PubMed
- Martín-Muñoz MF, Bartolome B, Caminoa M, et al. Bee pollen: a dangerous food for allergic children. Identification of responsible allergens. Allergol Immunopathol (Madr) 2010;38:263-5. PubMed
- Neef H, Cilli F, Declerck PJ, et al. Platelet anti-aggregating activity of Taraxacum officinale Weber. Phytotherapy Research 1996;10:s138-s140.
- Cuzzolin L, Zaffani S, and Benoni G. Safety implications regarding use of phytomedicines. Eur.J Clin Pharmacol. 2006;62:37-42. PubMed
- Posadzki, P., Watson, L. K., and Ernst, E. Adverse effects of herbal medicines: an overview of systematic reviews. Clin Med 2013;13(1):7-12. PubMed
- Wakelin, S. H., Marren, P., Young, E., and Shaw, S. Compositae sensitivity and chronic hand dermatitis in a seven-year-old boy. Br J Dermatol 1997;137(2):289-291. PubMed
- Ingber, A. Seasonal allergic contact dermatitis from Taraxacum officinale (dandelion) in an Israeli florist. Contact Dermatitis 2000;43(1):49.
- Rodriguez, B., Rodriguez, A., de Barrio, M., Tornero, P., and Baeza, M. L. Asthma induced by canary food mix. Allergy Asthma Proc. 2003;24(4):265-268.
- Syhaieva, I. A. [Efficiency of specific immunotherapy in treatment of patients with seasonal allergic rhinitis]. Lik.Sprava. 2006;(1-2):51-53.
- Catania, M. A., Oteri, A., Caiello, P., Russo, A., Salvo, F., Giustini, E. S., Caputi, A. P., and Polimeni, G. Hemorrhagic cystitis induced by an herbal mixture. South.Med.J. 2010;103(1):90-92. PubMed
- Goksu, E., Eken, C., Karadeniz, O., and Kucukyilmaz, O. First report of hypoglycemia secondary to dandelion (Taraxacum officinale) ingestion. Am J Emerg.Med 2010;28(1):111-112. PubMed
- Fernandez-Gonzalez, D., Gonzalez-Parrado, Z., Vega-Maray, A. M., Valencia-Barrera, R. M., Camazon-Izquierdo, B., De, Nuntiis P., and Mandrioli, P. Platanus pollen allergen, Pla a 1: quantification in the atmosphere and influence on a sensitizing populati
- Liang, K. L., Su, M. C., Shiao, J. Y., Wu, S. H., Li, Y. H., and Jiang, R. S. Role of pollen allergy in Taiwanese patients with allergic rhinitis. J Formos.Med Assoc. 2010;109(12):879-885. PubMed
- Yang, Y., Zhao, Y., Wang, C. S., Wang, X. D., and Zhang, L. [Prevalence of sensitization to aeroallergens in 10 030 patients with allergic rhinitis]. Zhonghua Er.Bi Yan.Hou Tou.Jing.Wai Ke Za Zhi 2011;46(11):914-920.
- Davies, M. G. and Kersey, P. J. Contact allergy to yarrow and dandelion. Contact Dermatitis 1986;14(4):256-257. PubMed
- Collins JM and Miller DR. Dandelion green bezoar following antrectomy and vagotomy - case report. J Kansas Med Soc 1966;67(6):303-304.
- Moriarty B, Pinney JH, Owen-Casey MP, Rustin MH, Deroide F, Laing C, Davenport A. Digital necrosis from dandelion tea. Br J Dermatol. 2013 Jul;169(1):227-30. PubMed
- Onal S, Timur S, Okutucu B, Zihnioglu F. Inhibition of alphaglucosidase by aqueous extracts of some potent antidiabetic medicinal herbs. Prep Biochem Biotechnol 2005;35:29-36.
Thiamine 7 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Rogovik, A. L., Vohra, S., and Goldman, R. D. Safety considerations and potential interactions of vitamins: should vitamins be considered drugs? Ann.Pharmacother. 2010;44(2):311-324. PubMed
- Arruti N, Bernedo N, Audicana MT, Villarreal O, Uriel O, Muñoz D. Systemic allergic dermatitis caused by thiamine after iontophoresis. Contact Dermatitis. 2013 Dec;69(6):375-6. PubMed
- Thiamine hydrochloride injection package insert. Lake Zurich, IL: Fresenius Kabi, LLC; September 2019.
- Vora B, Wen A, Yee SW, et al. The Effect of Trimethoprim on Thiamine Absorption: A Transporter-Mediated Drug-Nutrient Interaction. Clin Pharmacol Ther 2023;114(2):381-392.
N-acetyl Cysteine (nac) 86 references
- Ellenhorn MJ, et al. Ellenhorn's Medical Toxicology: Diagnoses and Treatment of Human Poisoning. 2nd ed. Baltimore, MD: Williams & Wilkins, 1997.
- Jepsen S, Hansen AB. The influence of N-acetylcysteine on the measurement of prothrombin time and activated partial thromboplastin time in healthy subjects. Scand J Clin Lab Invest 1994;54:543-7. PubMed
- van Zandwijk N, Dalesio O, Pastorino U, et al. EUROSCAN, a randomized trial of vitamin A and N-acetylcysteine in patients with head and neck cancer or lung cancer. For the European Organization for Research and Treatment of Cancer Head and Neck and Lung C DOI
- Horowitz RS, Dart RC, Jarvie DR, et al. Placental transfer of N-acetylcysteine following human maternal acetaminophen toxicity. J Toxicol Clin Toxicol 1997;35:447-51.
- Bailey B, McGuigan MA. Management of anaphylactoid reactions to intravenous N-acetylcysteine. Ann Emerg Med 1998;31:710-5. PubMed
- Spiller HA, Krenzelok EP, Grande GA, et al. A prospective evaluation of the effect of activated charcoal before oral N-acetylcysteine in acetaminophen overdose. Ann Emerg Med 1994;23:519-23. PubMed
- Ardissino D, Merlini PA, Savonitto S, et al. Effect of transdermal nitroglycerin or N-acetylcysteine, or both, in the long-term treatment of unstable angina pectoris. J Am Coll Cardiol 1997;29:941-7. PubMed
- Horowitz JD, Henry CA, Syrjanen ML, et al. Nitroglycerine/N-acetylcysteine in the management of unstable angina pectoris. Eur Heart J 1988;9:95-100. PubMed
- Louwerse ES, Weverling GJ, Bossuyt PM, et al. Randomized, double-blind, controlled trial of acetylcysteine in amyotrophic lateral sclerosis. Arch Neurol 1995;52:559-64. PubMed
- Wiklund O, Fager G, Andersson A, et al. N-acetylcysteine treatment lowers plasma homocysteine but not serum lipoprotein(a) levels. Atherosclerosis 1996;119:99-106. PubMed
- De Flora S, Grassi C, Carati L. Attenuation of influenza-like symptomatology and improvement of cell-mediated immunity with long-term N-acetylcysteine treatment. Eur Respir J 1997;10:1535-41. PubMed
- Iversen HK. N-acetylcysteine enhances nitroglycerin-induced headache and cranial arterial responses. Clin Pharmacol Ther 1992;52:125-33. PubMed
- Behr J, Maier K, Degenkolb B, et al. Antioxidative and clinical effects of high-dose N-acetylcysteine in fibrosing alveolitis. Adjunctive therapy to maintenance immunosuppression. Am J Respir Crit Care Med 1997;156:1897-901.
- Tenenbein PK, Sitar DS, Tenenbein M. Interaction between N-acetylcysteine and activated charcoal: implications for the treatment of acetaminophen poisoning. Pharmacotherapy 2001;21:1331-6.
- Arstall MA, Yang J, Stafford I, et al. N-acetylcysteine in combination with nitroglycerin and streptokinase for the treatment of evolving acute myocardial infarction. Safety and biochemical effects. Circulation 1995;92:2855-62.
- Estensen RD, Levy M, Klopp SJ, et al. N-acetylcysteine suppression of the proliferative index in the colon of patients with previous adenomatous colonic polyps. Cancer Lett 1999;147:109-14. PubMed
- Pela R, Calcagni AM, Subiaco S, et al. N-acetylcysteine reduces the exacerbation rate in patients with moderate to severe COPD. Respiration 1999;66:495-500.. PubMed
- Oldemeyer JB, Biddle WP, Wurdeman RL, et al. Acetylcysteine in the prevention of contrast-induced nephropathy after coronary angiography. Am Heart J 2003;146:E23. . PubMed
- Ekins BR, Ford DC, Thompson MI, et al. The effect of activated charcoal on N-acetylcysteine absorption in normal subjects. Am J Emerg Med. 1987;5(6):483-7. PubMed
- Chamberlain JM, Gorman RL, Oderda GM, Klein-Schwartz W, Klein BL. Use of activated charcoal in a simulated poisoning with acetaminophen: a new loading dose for N-acetylcysteine? Ann Emerg Med. 1993;22(9):1398-402. PubMed
- Renzi FP, Donovan JW, Martin TG, Morgan L, Harrison EF. Concomitant use of activated charcoal and N-acetylcysteine. Ann Emerg Med. 1985;14(6):568-72. DOI
- North DS, Peterson RG, Krenzelok EP. Effect of activated charcoal administration on acetylcysteine serum levels in humans. Am J Hosp Pharm. 1981;38(7):1022-4. DOI
- Loscalzo J. N-Acetylcysteine potentiates inhibition of platelet aggregation by nitroglycerin. J Clin Invest. 1985;76(2):703-8. PubMed
- Ruiz FJ, Salom MG, Inglés AC, et al. N-acetyl-L-cysteine potentiates depressor response to captopril and enalaprilat in SHRs. Am J Physiol. 1994;267(3 Pt 2):R767-72. PubMed
- Deharo E, Barkan D, Krugliak M, Golenser J, Ginsburg H. Potentiation of the antimalarial action of chloroquine in rodent malaria by drugs known to reduce cellular glutathione levels. Biochem Pharmacol. 2003;66(5):809-17. PubMed
- Buckley, N. A., Whyte, I. M., O'Connell, D. L., and Dawson, A. H. Oral or intravenous N-acetylcysteine: which is the treatment of choice for acetaminophen (paracetamol) poisoning? J Toxicol.Clin Toxicol. 1999;37(6):759-767.
- Sunman, W., Hughes, A. D., and Sever, P. S. Anaphylactoid response to intravenous acetylcysteine. Lancet 5-16-1992;339(8803):1231-1232. PubMed
- Reynard, K., Riley, A., and Walker, B. E. Respiratory arrest after N-acetylcysteine for paracetamol overdose. Lancet 9-12-1992;340(8820):675. PubMed
- BERNSTEIN, I. L. and AUSDENMOORE, R. W. IATROGENIC BRONCHOSPASM OCCURRING DURING CLINICAL TRIALS OF A NEW MUCOLYTIC AGENT, ACETYLCYSTEINE. Dis.Chest 1964;46:469-473. PubMed
- REAS, H. W. THE USE OF N-ACETYLCYSTEINE IN THE TREATMENT OF CYSTIC FIBROSIS. J Pediatr 1964;65:542-557. PubMed
- Bibi, H., Seifert, B., Oullette, M., and Belik, J. Intratracheal N-acetylcysteine use in infants with chronic lung disease. Acta Paediatr. 1992;81(4):335-339. PubMed
- Jepsen, S., Herlevsen, P., Knudsen, P., Bud, M. I., and Klausen, N. O. Antioxidant treatment with N-acetylcysteine during adult respiratory distress syndrome: a prospective, randomized, placebo-controlled study. Crit Care Med 1992;20(7):918-923. PubMed
- Roes, E. M., Raijmakers, M. T., Boo, T. M., Zusterzeel, P. L., Merkus, H. M., Peters, W. H., and Steegers, E. A. Oral N-acetylcysteine administration does not stabilise the process of established severe preeclampsia. Eur.J Obstet.Gynecol.Reprod.Biol 2006
- Spiller, H. A., Winter, M. L., Klein-Schwartz, W., and Bangh, S. A. Efficacy of activated charcoal administered more than four hours after acetaminophen overdose. J Emerg.Med 2006;30(1):1-5. PubMed
- Tirouvanziam, R., Conrad, C. K., Bottiglieri, T., Herzenberg, L. A., Moss, R. B., and Herzenberg, L. A. High-dose oral N-acetylcysteine, a glutathione prodrug, modulates inflammation in cystic fibrosis. Proc Natl.Acad.Sci U.S.A 3-21-2006;103(12):4628-463
- Niemi, T. T., Munsterhjelm, E., Poyhia, R., Hynninen, M. S., and Salmenpera, M. T. The effect of N-acetylcysteine on blood coagulation and platelet function in patients undergoing open repair of abdominal aortic aneurysm. Blood Coagul.Fibrinolysis 2006;1 PubMed
- Komisarof, J. A., Gilkey, G. M., Peters, D. M., Koudelka, C. W., Meyer, M. M., and Smith, S. M. N-acetylcysteine for patients with prolonged hypotension as prophylaxis for acute renal failure (NEPHRON). Crit Care Med 2007;35(2):435-441. PubMed
- Grimble, G. K. Adverse gastrointestinal effects of arginine and related amino acids. J Nutr 2007;137(6 Suppl 2):1693S-1701S. PubMed
- Berk, M., Copolov, D. L., Dean, O., Lu, K., Jeavons, S., Schapkaitz, I., Anderson-Hunt, M., and Bush, A. I. N-acetyl cysteine for depressive symptoms in bipolar disorder--a double-blind randomized placebo-controlled trial. Biol Psychiatry 9-15-2008;64(6) PubMed
- Shahin, A. Y., Hassanin, I. M., Ismail, A. M., Kruessel, J. S., and Hirchenhain, J. Effect of oral N-acetyl cysteine on recurrent preterm labor following treatment for bacterial vaginosis. Int J Gynaecol.Obstet. 2009;104(1):44-48. PubMed
- Nigwekar, S. U. and Kandula, P. N-acetylcysteine in cardiovascular-surgery-associated renal failure: a meta-analysis. Ann Thorac.Surg 2009;87(1):139-147. PubMed
- Sandilands, E. A. and Bateman, D. N. Adverse reactions associated with acetylcysteine. Clin Toxicol.(Phila) 2009;47(2):81-88. PubMed
- Wijeysundera, D. N., Karkouti, K., Rao, V., Granton, J. T., Chan, C. T., Raban, R., Carroll, J., Poonawala, H., and Beattie, W. S. N-acetylcysteine is associated with increased blood loss and blood product utilization during cardiac surgery. Crit Care Me PubMed
- Holdiness, M. R. Clinical pharmacokinetics of N-acetylcysteine. Clin Pharmacokinet. 1991;20(2):123-134. PubMed
- Dawson, A. H., Henry, D. A., and McEwen, J. Adverse reactions to N-acetylcysteine during treatment for paracetamol poisoning. Med J Aust. 3-20-1989;150(6):329-331.
- Rasmussen, J. B. and Glennow, C. Reduction in days of illness after long-term treatment with N-acetylcysteine controlled-release tablets in patients with chronic bronchitis. Eur.Respir.J 1988;1(4):351-355. DOI
- Walters, M. T., Rubin, C. E., Keightley, S. J., Ward, C. D., and Cawley, M. I. A double-blind, cross-over, study of oral N-acetylcysteine in Sjogren's syndrome. Scand J Rheumatol.Suppl 1986;61:253-258.
- Cato, A., Goldstein, I., and Millman, M. A double-blind parallel study of acetylcysteine-isoproterenol and saline-isoproterenol in patients with chronic obstructive lung disease. J Int Med Res 1977;5(3):175-183. PubMed
- Parr, G. D. and Huitson, A. Oral Fabrol (oral N-acetyl-cysteine) in chronic bronchitis. Br.J.Dis.Chest 1987;81(4):341-348.
- Dano, G. Bronchospasm caused by acetylcysteine in children with bronchial asthma. Acta Allergol. 1971;26(3):181-190. DOI
- Howatt, W. F. and DeMuth, G. R. A double-blind study of the use of acetylcysteine in patients with cystic fibrosis. Univ Mich.Med Cent.J 1966;32(2):82-85.
- Millman, M. and Grundon, W. Use of acetylcysteine in bronchial asthma and emphysema. J Asthma Res 1969;6(4):199-209. PubMed
- Vale, J. A. and Wheeler, D. C. Anaphylactoid reaction to acetylcysteine. Lancet 10-30-1982;2(8305):988.
- Mant, T. G., Tempowski, J. H., Volans, G. N., and Talbot, J. C. Adverse reactions to acetylcysteine and effects of overdose. Br Med J (Clin Res Ed) 7-28-1984;289(6439):217-219. PubMed
- Myers, C., Bonow, R., Palmeri, S., Jenkins, J., Corden, B., Locker, G., Doroshow, J., and Epstein, S. A randomized controlled trial assessing the prevention of doxorubicin cardiomyopathy by N-acetylcysteine. Semin.Oncol 1983;10(1 Suppl 1):53-55.
- Miller, L. F. and Rumack, B. H. Clinical safety of high oral doses of acetylcysteine. Semin.Oncol 1983;10(1 Suppl 1):76-85.
- Boman, G., Backer, U., Larsson, S., Melander, B., and Wahlander, L. Oral acetylcysteine reduces exacerbation rate in chronic bronchitis: report of a trial organized by the Swedish Society for Pulmonary Diseases. Eur J Respir.Dis 1983;64(6):405-415.
- Tattersall, A. B., Bridgman, K. M., and Huitson, A. Irish general practice study of acetylcysteine (Fabrol) in chronic bronchitis. J Int Med Res 1984;12(2):96-101. PubMed
- Jackson, I. M., Barnes, J., and Cooksey, P. Efficacy and tolerability of oral acetylcysteine (Fabrol) in chronic bronchitis: a double-blind placebo controlled study. J Int Med Res 1984;12(3):198-206. PubMed
- Ho, S. W. and Beilin, L. J. Asthma associated with N-acetylcysteine infusion and paracetamol poisoning: report of two cases. Br Med J (Clin Res Ed) 9-24-1983;287(6396):876-877. PubMed
- Vale, J. A. and Buckley, B. M. Asthma associated with N-acetylcysteine infusion and paracetamol poisoning. Br Med J (Clin Res Ed) 10-22-1983;287(6400):1223. PubMed
- Bateman, D. N., Woodhouse, K. W., and Rawlins, M. D. Adverse reactions to N-acetylcysteine. Hum Toxicol. 1984;3(5):393-398. PubMed
- Gervais, S., Lussier-Labelle, F., and Beaudet, G. Anaphylactoid reaction to acetylcysteine. Clin Pharm 1984;3(6):586-587.
- Tattersall, A. B., Bridgman, K. M., and Huitson, A. Acetylcysteine (Fabrol) in chronic bronchitis--a study in general practice. J Int Med Res 1983;11(5):279-284. PubMed
- Casola, G. and vanSonnenberg, E. Skin damage from acetylcysteine leak during percutaneous abscess drainage. Radiology 1984;152(1):233. PubMed
- Aylward, M., Maddock, J., and Dewland, P. Clinical evaluation of acetylcysteine in the treatment of patients with chronic obstructive bronchitis: a balanced double-blind trial with placebo control. Eur.J Respir.Dis.Suppl 1980;111:81-89.
- Long-term oral acetylcysteine in chronic bronchitis. a double-blind controlled study. Eur.J Respir.Dis.Suppl 1980;111:93-108.
- Chan, T. Y. and Critchley, J. A. Adverse reactions to intravenous N-acetylcysteine in Chinese patients with paracetamol (acetaminophen) poisoning. Hum Exp.Toxicol. 1994;13(8):542-544. PubMed
- Hansen, N. C., Skriver, A., Brorsen-Riis, L., Balslov, S., Evald, T., Maltbaek, N., Gunnersen, G., Garsdal, P., Sander, P., Pedersen, J. Z., and . Orally administered N-acetylcysteine may improve general well-being in patients with mild chronic bronchiti
- Reid, M. B., Stokic, D. S., Koch, S. M., Khawli, F. A., and Leis, A. A. N-acetylcysteine inhibits muscle fatigue in humans. J Clin Invest 1994;94(6):2468-2474. PubMed
- Chirkov, Y. Y. and Horowitz, J. D. N-Acetylcysteine potentiates nitroglycerin-induced reversal of platelet aggregation. J Cardiovasc.Pharmacol 1996;28(3):375-380. PubMed
- Hershkovitz, E., Shorer, Z., Levitas, A., and Tal, A. Status epilepticus following intravenous N-acetylcysteine therapy. Isr.J Med Sci 1996;32(11):1102-1104.
- Stavem, K. [Anaphylactic reaction to N-acetylcysteine after poisoning with paracetamol]. Tidsskr.Nor Laegeforen. 5-30-1997;117(14):2038-2039.
- Walton, N. G., Mann, T. A., and Shaw, K. M. Anaphylactoid reaction to N-acetylcysteine. Lancet 12-15-1979;2(8155):1298. PubMed
- Perry, H. E. and Shannon, M. W. Efficacy of oral versus intravenous N-acetylcysteine in acetaminophen overdose: results of an open-label, clinical trial. J Pediatr 1998;132(1):149-152. PubMed
- Kory, R. C., Hirsch, S. R., and Giraldo, J. Nebulization of N-acetylcysteine combined with a bronchodilator in patients with chronic bronchitis. A controlled study. Chest 1968;54(6):504-509. PubMed
- Nahir, A. M., Scharf, J. M., and Szargel, R. Effects of oral N-acetylcysteine on both ocular and oral manifestations of Sjogren's Syndrome. Curr Ther Res 1989;46:187-192.
- Charley, G., Dean, B. S., and Krenzelok, E. P. Oral N-acetylcysteine-induced urticaria: a case report. Vet.Hum Toxicol. 1987;29:477.
- Jenkins DD, Wiest DB, Mulvihill DM, et al. Fetal and neonatal effects of N-acetylcysteine when used for neuroprotection in maternal chorioamnionitis. J Pediatr. 2016 Jan;168:67-76.e6. PubMed
- Costa DLC, Diniz JB, Requena G, et al. Randomized double-blind, placebo-controlled trial of N-acetylcysteine augmentation for treatment-resistant obsessive-compulsive disorder. J Clin Psychiatry. 2017 Jul;78(7):e799-e773.
- Kranzer K, Elamin WF, Cox H, Seddon JA, Ford N, Drobniewski F. A systematic review and meta-analysis of the efficacy and safety of N-acetylcysteine in preventing aminoglycoside-induced ototoxicity: implications for the treatment of multidrug-resistant TB.
- Wang W, Zhang Y, Liu Y, Xu L, Shi D. Severe chest pain due to N-acetylcysteine-induced esophagitis. Case Rep Med. 2019;2019:8057259.
- Li F, Welling MC, Johnson JA, et al. N-acetylcysteine for pediatric obsessive-compulsive disorder: A small pilot study. J Child Adolesc Psychopharmacol. 2020;30(1):32-37. PubMed
- Monti DA, Zabrecky G, Leist TP, et al. N-acetyl cysteine administration is associated with increased cerebral glucose metabolism in patients with multiple sclerosis: An exploratory study. Front Neurol. 2020;11:88. PubMed
- Gray KM, Carpenter MJ, Baker NL, et al. A double-blind randomized controlled trial of N-acetylcysteine in cannabis-dependent adolescents. Am J Psychiatry. 2012;169(8):805-12.
- Sarris J, Byrne G, Castle D, et al. N-acetyl cysteine (NAC) augmentation in the treatment of obsessive-compulsive disorder: A phase III, 20-week, double-blind, randomized, placebo-controlled trial. Prog Neuropsychopharmacol Biol Psychiatry 2022;117:110550 PubMed
See these in context on the N-acetyl Cysteine (nac) monograph →
Glutathione 1 reference
- Marrades RM, Roca J, Barbera JA, et al. Nebulized glutathione induces bronchoconstriction in patients with mild asthma. Am J Respir Crit Care Med 1997;156(2 Pt 1):425-30. PubMed
Methionine 12 references
- La Vecchia C, Negri E, Franceschi S, Decarli A. Case-control study on influence of methionine, nitrite, and salt on gastric carcinogenesis in northern Italy. Nutr Cancer 1997;27:65-8. PubMed
- Btaiche IF, Khalidi N. Parenteral nutrition-associated liver complications in children. Pharmacotherapy 2002;22:188-211.. PubMed
- Cottington EM, LaMantia C, Stabler SP, et al. Adverse event associated with methionine loading test: a case report. Arterioscler Thromb Vasc Biol 2002;22:1046-50.. PubMed
- Anon. Should methionine be added to paracetamol formulations? Drug Ther Perspect 1997;10:11-3. DOI
- Smulders, Y. M., Rakic, M., Slaats, E. H., Treskes, M., Sijbrands, E. J., Odekerken, D. A., Stehouwer, C. D., and Silberbusch, J. Fasting and post-methionine homocysteine levels in NIDDM. Determinants and correlations with retinopathy, albuminuria, and c
- McAuley, D. F., Hanratty, C. G., McGurk, C., Nugent, A. G., and Johnston, G. D. Effect of methionine supplementation on endothelial function, plasma homocysteine, and lipid peroxidation. J.Toxicol.Clin.Toxicol. 1999;37(4):435-440. PubMed
- Hanratty, C. G., McGrath, L. T., McAuley, D. F., Young, I. S., and Johnston, G. D. The effects of oral methionine and homocysteine on endothelial function. Heart 2001;85(3):326-330. PubMed
- Ward, M., McNulty, H., McPartlin, J., Strain, J. J., Weir, D. G., and Scott, J. M. Effect of supplemental methionine on plasma homocysteine concentrations in healthy men: a preliminary study. Int.J.Vitam.Nutr.Res. 2001;71(1):82-86. PubMed
- Yaghmai, R., Kashani, A. H., Geraghty, M. T., Okoh, J., Pomper, M., Tangerman, A., Wagner, C., Stabler, S. P., Allen, R. H., Mudd, S. H., and Braverman, N. Progressive cerebral edema associated with high methionine levels and betaine therapy in a patient
- Talukdar R, Murthy HV, Reddy DN. Role of methionine containing antioxidant combination in the management of pain in chronic pancreatitis: a systematic review and meta-analysis. Pancreatology 2015;15(2):136-44. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Energy, Carbohydrate, Fiber, Fat, Fatty Acids, Cholesterol, Protein, and Amino Acids. Washington, DC: The National Academies Press, 2005. Available at: https://doi.org/10.17226 DOI
- Khairan P, Sobue T, Eshak ES, et al. Association of B Vitamins and Methionine Intake with the Risk of Gastric Cancer: The Japan Public Health Center-based Prospective Study. Cancer Prev Res (Phila) 2022;15(2):101-110. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC