
EyeCare+ Ingredients & Drug Interactions
by Herbs SRA
What is this page for?
First and foremost: checking EyeCare+ against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
EyeCare+ is a dietary supplement by Herbs SRA with 7 active ingredients. Its ingredients are commonly taken for common cold and immune support, antioxidant support, skin health and collagen formation.Based on those ingredients, 1,044 medications have a known interaction with it, the most serious rated moderate. The ingredients most likely to interact are Vitamin E, Omega-3, Bilberry extract. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against EyeCare+ by Herbs SRA
Ask about any prescription or over-the-counter medication and we check it for interactions with EyeCare+ by Herbs SRA — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of EyeCare+ by Herbs SRA
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
EyeCare+ contains seven active ingredients. Vitamin C supports immune function and serves other roles in the body.
Copper is a mineral needed for various enzymatic processes. Vitamin E is a fat-soluble antioxidant.
Coenzyme Q10 is a compound involved in cellular energy production. Bilberry extract comes from the fruit of the bilberry plant.
Eyebright aerial part extract is derived from the above-ground portions of the eyebright herb. Omega-3 is also included, though we have no interaction data on file for it.
The capsules also contain cellulose as an inactive ingredient.
Does it work?
Moderate evidence
The evidence for most of EyeCare+'s ingredients in supporting eye health specifically is not established in our data. For the individual ingredients themselves: vitamin C is effective for vitamin C deficiency and possibly effective for conditions including cataracts and exercise-induced respiratory infections.
Vitamin E is effective for vitamin E deficiency and possibly effective for Alzheimer disease and several other conditions. Coenzyme Q10 is likely effective for CoQ10 deficiency and possibly effective for fibromyalgia, migraines, and heart failure.
Bilberry's effectiveness for night vision is rated possibly ineffective, and evidence for its use in age-related macular degeneration and other eye or brain conditions is insufficient. Eyebright has insufficient evidence for the conditions it's traditionally used for, including eye irritation and respiratory complaints.
The evidence for this combination as an eye-care product overall is not on file.
How safe is it?
Well-documented data
Vitamin C is generally well tolerated at normal doses, but very high doses can cause side effects including abdominal cramps, diarrhea, heartburn, and kidney stones (especially in people prone to them). Adverse effects are more likely above 2 grams daily.
Copper is safe in amounts found in food and standard supplements, but excess copper can be toxic. Vitamin E at usual dietary amounts is safe, but high-dose long-term supplements may increase bleeding risk.
Coenzyme Q10 is generally well tolerated, with gastrointestinal side effects (appetite suppression, diarrhea, nausea) occurring in less than 1% of patients. Bilberry fruit is generally well tolerated, though concentrated supplements have limited safety data; common side effects include flatulence and dark-colored stools.
Eyebright has been reported to cause confusion, headache, nausea, constipation, and cough. For pregnancy: Vitamin C in normal amounts from food and prenatal vitamins is fine, but avoid high-dose supplements.
Bilberry fruit is likely safe in pregnancy. Eyebright safety data advises against use in pregnancy.
Copper and Vitamin E have no pregnancy rating on file — talk with your doctor. For breastfeeding: Vitamin E in normal dietary amounts is considered fine; avoid high-dose supplements.
Bilberry and Coenzyme Q10 safety while breastfeeding is not well studied — check with your doctor. Eyebright should be avoided while breastfeeding.
Meds to double-check
Moderate interaction found
Before taking EyeCare+, have your pharmacist check the following medication types: blood thinners and anticoagulants (like warfarin) — moderate risk of increased bleeding from vitamin C and E, and warfarin interaction with coenzyme Q10; estrogen-based birth control or hormone replacement therapy — vitamin C may increase estrogen levels; diabetes medications — both bilberry and eyebright may lower blood sugar; chemotherapy drugs, especially alkylating agents and antitumor antibiotics — antioxidants in vitamin C and E may reduce their effectiveness; cyclosporine (an immunosuppressant) — vitamin E may increase its levels; and HIV medications like indinavir. Additionally, check medications metabolized by your liver (CYP3A4 and CYP2E1), antipsychotics like fluphenazine, levothyroxine for thyroid, and blood pressure medications.
No interactions are documented for omega-3 among the ingredients we could check.
The bottom line
Scorecard at a glanceFully disclosed formula with some supporting evidence for its stated purpose. Moderate medication interactions have been identified, and safety information is well characterized.
EyeCare+ combines popular eye-support herbs and vitamins, but the evidence for their effectiveness as an eye-care product is limited or not established in our data. If you take warfarin, blood thinners, birth control pills, hormone therapy, diabetes medications, or chemotherapy, you should check your specific medications before starting this product because several ingredients interact with them.
Talk with your pharmacist before adding EyeCare+ to your routine, especially if you're pregnant, breastfeeding, or taking any prescription medications.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 7 of 7 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jul 25, 2024.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about EyeCare+, straight from the product label.
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
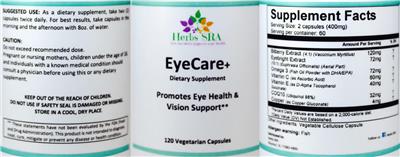
Supplement Facts
The label details for EyeCare+ by Herbs SRA, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Vitamin C | 60 mg | -- |
| Copper | 4 mg | -- |
| Vitamin E | 40 mg | -- |
| Coenzyme Q-10 | 32 mg | -- |
| Bilberry extract | 120 mg | -- |
| Eyebright Aerial Part Extract | 72 mg | -- |
| Omega-3 | 72 mg | -- |
Other ingredients: Cellulose
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Suggested/Recommended/Usage/Directions
Suggested Use: As a dietary supplement, take two (2) capsules twice daily. For best results, take capsules in the morning and the afternoon with 8 oz. of water.
Precautions
Caution: Do not exceed recommended dose.
Pregnant or nursing mothers, children under the age of 18 and individuals with a known medical condition should consult a physician before using this or any dietary supplement.
Pregnant or nursing mothers, children under the age of 18 and individuals with a known medical condition should consult a physician before using this or any dietary supplement. Keep out of reach of children.
Do not use if safety seal is damaged or missing.
Allergen Warning: Fish
Storage
Store in a cool, dry place.
FDA Disclaimer Statement
These statements have not been evaluated by the FDA (Food and Drug Administration). This product is not intended to diagnose, treat, cure, mitigate or prevent any disease or health condition.
FDA Statement of Identity
Dietary Supplement
Formulation
Promotes Eye Health & Vision Support
General Statements
Follow us: Facebook Herbs SRA
Herbs SRA Let the Herbs Improve Your Health
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
EyeCare+ by Herbs SRA label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in EyeCare+ by Herbs SRA
These are the 7 active ingredients this product is made of. Select any to open its full monograph.
Serving size400 mg Dosage formCapsule Servings per container60 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Vitamin C
Interacts with207 drugs
Vitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for im...
Vitamin C monograph & interactionsCopper
Interacts with31 drugs
Copper is an essential trace mineral your body needs in small amounts for making red blood cells, supporting nerves and bones, and helping enzymes wor...
Copper monograph & interactionsVitamin E
Interacts with764 drugs
Vitamin E is an essential fat-soluble vitamin and antioxidant that most people get in adequate amounts from a normal diet. Supplements can help correc...
Vitamin E monograph & interactionsCoenzyme Q-10
Interacts with198 drugs
CoQ10 is a vitamin-like substance your body makes naturally that helps cells produce energy and acts as an antioxidant. It is generally well tolerated...
Coenzyme Q-10 monograph & interactionsBilberry extract
Interacts with275 drugs
Bilberry is a blueberry-like fruit rich in antioxidant plant compounds called anthocyanins, and it has a long history of traditional use for eye healt...
Bilberry extract monograph & interactionsEyebright Aerial Part Extract
Interacts with86 drugs
Eyebright is a traditional herb long used for minor eye irritation, redness, and allergy symptoms, but high-quality human studies are very limited. Th...
Eyebright Aerial Part Extract monograph & interactionsOmega-3
Interacts with375 drugs
DHA is an omega-3 fatty acid found in fatty fish and algae that is a building block for the brain, nervous system, and eyes. It is widely used and gen...
Omega-3 monograph & interactionsOther (inactive) ingredients: Cellulose. These complete the product’s ingredient list but are not active constituents.
EyeCare+ by Herbs SRA Drug Interactions
HelloPharmacist Interaction Report
EyeCare+ by Herbs SRA contains several ingredients with documented interactions with medications.
Vitamin C, one of the active ingredients, has the most serious interactions — it can moderately reduce the effectiveness of warfarin (a blood thinner), potentially lowering your clotting ability and putting you at risk.
Read the full breakdown — every affected drug type, severity by severity
Vitamin C also interacts moderately with estrogens (including birth control pills and hormone therapy), potentially increasing estrogen blood levels; chemotherapy drugs called alkylating agents, where vitamin C's antioxidant effects might reduce their cancer-fighting power; and several others including the antibiotic levothyroxine, the HIV medication indinavir, and the antipsychotic fluphenazine. Vitamin E in this product carries moderate interactions with blood thinners and anticoagulants (increasing bleeding risk), warfarin, chemotherapy drugs, and cyclosporine (an immunosuppressant).
Coenzyme Q10 may interact moderately with warfarin and alkylating chemotherapy agents, and can theoretically lower blood pressure when combined with blood pressure medications.
Bilberry extract has moderate interactions with blood thinners, diabetes medications, and the cancer drug erlotinib. Eyebright may increase low blood sugar risk (hypoglycemia) with diabetes medications.
Altogether, these interactions span 1,032 individual medications.
Omega-3 is listed as an ingredient, but we hold no interaction data for it. Check your exact medications with the tool on this page before starting EyeCare+.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against EyeCare+?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in EyeCare+ interact with 1,044 drugs. Click any drug to see the details.
7 of the 7 ingredients in EyeCare+ interact with drugs. Each result below shows which ingredient is responsible. Vitamin E Omega-3 Bilberry extract Vitamin C Coenzyme Q-10 Eyebright Aerial Part Extract Copper
Ado-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with EyeCare+ — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Ado-trastuzumab Emtansine interactionAbciximabReoPro
How Abciximab interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Vitamin EAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Read the full Vitamin E + Abciximab interactionOmega-3Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, DHA may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Omega-3 + Abciximab interactionBilberry ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, bilberry fruit extract might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full Bilberry Extract + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with EyeCare+ — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Abemaciclib interactionAbiraterone
How Abiraterone interacts with EyeCare+ — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with EyeCare+ — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Vitamin EAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Read the full Vitamin E + Abrocitinib interactionBilberry ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, bilberry fruit extract might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full Bilberry Extract + Abrocitinib interactionOmega-3Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, DHA may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Omega-3 + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with EyeCare+ — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Omega-3Antidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking DHA with antidiabetes drugs might reduce the effects of these medications.
Read the full Omega-3 + Acarbose interactionEyebright Aerial Part ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, eyebright might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Read the full Eyebright Aerial Part Extract + Acarbose interactionBilberry ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, bilberry leaf or fruit extract may increase the risk of hypoglycemia when taken with antidiabetes drugs.
Read the full Bilberry Extract + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with EyeCare+ — through 2 ingredients. Tap an ingredient for the detail:
Omega-3Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking DHA with antihypertensive drugs might increase the risk of hypotension.
Read the full Omega-3 + Acebutolol interactionCoenzyme Q-10Antihypertensive Drugs Minor
Interaction Summary
Theoretically, coenzyme Q10 might have additive effects with antihypertensive drugs.
Read the full Coenzyme Q-10 + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Bilberry ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, bilberry fruit extract might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full Bilberry Extract + Acenocoumarol interactionOmega-3Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, DHA may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Omega-3 + Acenocoumarol interactionVitamin EAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Read the full Vitamin E + Acenocoumarol interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with EyeCare+ — through 2 ingredients. Tap an ingredient for the detail:
Bilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with EyeCare+ — through 4 ingredients. Tap an ingredient for the detail:
Bilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Aspirin interactionVitamin EAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Read the full Vitamin E + Acetaminophen, Aspirin interactionOmega-3Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, DHA may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Omega-3 + Acetaminophen, Aspirin interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with EyeCare+ — through 4 ingredients. Tap an ingredient for the detail:
Bilberry ExtractAnticoagulant/antiplatelet Drugs, Cytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full Bilberry Extract + Acetaminophen, Aspirin, Caffeine interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Aspirin, Caffeine interactionOmega-3Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, DHA may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Omega-3 + Acetaminophen, Aspirin, Caffeine interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with EyeCare+ — through 2 ingredients. Tap an ingredient for the detail:
Bilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, ButalbitalAxocet, Bancap, Bucet, Butex Forte, Esgic CF, Orbivan CF +5 more
How Acetaminophen, Butalbital interacts with EyeCare+ — through 2 ingredients. Tap an ingredient for the detail:
Bilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Butalbital interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Bilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Butalbital, Caffeine interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Butalbital, Caffeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Butalbital, Caffeine, Codeine interactionBilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with EyeCare+ — through 2 ingredients. Tap an ingredient for the detail:
Bilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Butalbital, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with EyeCare+ — through 2 ingredients. Tap an ingredient for the detail:
Bilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Bilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Bilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Caffeine, Codeine interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Caffeine, Codeine, Salicylamide interactionBilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Bilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Caffeine, Dihydrocodeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Caffeine, IsomethepteneMigralam
How Acetaminophen, Caffeine, Isometheptene interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Bilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Caffeine, Isometheptene interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Caffeine, Isometheptene interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Isometheptene interactionAcetaminophen, Caffeine, PyrilamineMidol Max Strength Menstrual
How Acetaminophen, Caffeine, Pyrilamine interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Caffeine, Pyrilamine interactionBilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Caffeine, Pyrilamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Pyrilamine interactionAcetaminophen, Chlorpheniramine Maleate, Dextromethorphan HbrVicks Formula 44M Cough, Cold & Flu Relief
How Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Bilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Vitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionBilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionAcetaminophen, Chlorpheniramine, DextromethorphanCoricidin II Extra Strength Cold and Flu
How Acetaminophen, Chlorpheniramine, Dextromethorphan interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Bilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionAcetaminophen, Chlorpheniramine, Dextromethorphan HydrobromideCoricidin HBP Maximum Strength Flu
How Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Bilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionAcetaminophen, Chlorpheniramine, Dextromethorphan, PhenylpropanolamineMulti Symptom Cold Relief
How Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interacts with EyeCare+ — through 3 ingredients. Tap an ingredient for the detail:
Bilberry ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Read the full Bilberry Extract + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionVitamin ECytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in EyeCare+ with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Vitamin E
Alkylating Agents
Theoretically, antioxidant effects of vitamin E might reduce the effectiveness of alkylating agents.
There's concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin E have on chemotherapy. Advise patients to consult their oncologist before using vitamin E supplements, especially in high doses.
Anticoagulant/Antiplatelet Drugs
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Vitamin E seems to inhibit of platelet aggregation and antagonize the effects of vitamin K-dependent clotting factors. These effects appear to be dose-dependent, and are probably only likely to be clinically significant with doses of at least 800 units daily. Mixed tocopherols, such as those found in food, might have a greater antiplatelet effect than alpha-tocopherol. RRR alpha-tocopherol (natural vitamin E) 1000 IU daily antagonizes vitamin K-dependent clotting factors. Advise patients to avoid high doses of vitamin E, especially in people with low vitamin K intake or other risk factors for bleeding.
Antitumor Antibiotics
Theoretically, antioxidant effects of vitamin E might reduce the effectiveness of antitumor antibiotics.
There's concern that antioxidants could reduce the activity of antitumor antibiotic drugs such as doxorubicin, which generate free radicals. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin E have on chemotherapy involving antitumor antibiotics. Advise patients to consult their oncologist before using vitamin E supplements, especially in high doses.
Cyclosporine (Neoral, Sandimmune)
A specific form of vitamin E might increase absorption and levels of cyclosporine.
There is some evidence that one specific formulation of vitamin E (D-alpha-tocopheryl-polyethylene glycol-1000 succinate, TPGS, tocophersolan, Liqui-E) might increase absorption of cyclosporine. This vitamin E formulation forms micelles which seems to increase absorption of cyclosporine by 40% to 72% in some patients. However, this interaction is unlikely to occur with the usual forms of vitamin E.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Vitamin E appears to bind with the nuclear receptor, pregnane X receptor (PXR), which results in increased expression of CYP3A4. Although the clinical significance of this is not known, use caution when considering concomitant use of vitamin E and other drugs affected by these enzymes.
Selumetinib (Koselugo)
Taking selumetinib with vitamin E can result in a total daily dose of vitamin E that exceeds safe limits and therefore might increase the risk of bleeding.
Selumetinib contains 48-54 IU vitamin E per capsule. The increased risk of bleeding with vitamin E appears to be dose-dependent. Be cautious when using selumetinib in combination with supplemental vitamin E, especially in patients at higher risk of bleed, such as those with chronic conditions and those taking antiplatelet drugs.
Warfarin (Coumadin)
Using vitamin E with warfarin might increase the risk of bleeding.
Due to interference with production of vitamin K-dependent clotting factors, use of more than 400 IU of vitamin E daily with warfarin might increase prothrombin time (PT), INR, and the risk of bleeding,. At a dose of 1000 IU per day, vitamin E can antagonize vitamin K-dependent clotting factors even in people not taking warfarin. Limited clinical evidence suggests that doses up to 1200 IU daily may be used safely by patients taking warfarin, but this may not be applicable in all patient populations.
Niacin
Vitamin E might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises high-density lipoprotein (HDL) cholesterol levels in people with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50%. Vitamin E alone combined with a statin does not seem to decrease HDL levels. It is not known whether the adverse effect on HDL is due to one of the other antioxidants or to the combination. It also is not known whether it will occur in other patient populations.
Omega-3
Anticoagulant/Antiplatelet Drugs
Theoretically, DHA may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Although some clinical evidence suggests that DHA might reduce collagen-stimulated platelet aggregation and thromboxane release, most clinical evidence suggests that DHA alone does not affect blood clotting. However, theoretically, when given in combination with EPA as fish oil, concomitant use with anticoagulant or antiplatelet drugs (including aspirin) might increase risk of bleeding.
Antidiabetes Drugs
Theoretically, taking DHA with antidiabetes drugs might reduce the effects of these medications.
In people with type 2 diabetes, including those taking oral hypoglycemic medications, DHA seems to increase fasting blood glucose levels.
Antihypertensive Drugs
Theoretically, taking DHA with antihypertensive drugs might increase the risk of hypotension.
Fish oils containing DHA can lower blood pressure and might have additive effects in patients treated with antihypertensives; use with caution.
Bilberry extract
Anticoagulant/Antiplatelet Drugs
Theoretically, bilberry fruit extract might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
In vitro, animal, and clinical research suggest that anthocyanidin extracts from bilberry can inhibit platelet aggregation.
Antidiabetes Drugs
Theoretically, bilberry leaf or fruit extract may increase the risk of hypoglycemia when taken with antidiabetes drugs.
Animal research suggests that bilberry leaf extract might have blood glucose-lowering activity. Also, one small clinical trial in patients with type 2 diabetes shows that taking bilberry fruit extract 470 mg as a single dose prior to an oral glucose tolerance test lowers plasma glucose levels when compared with placebo.
Cytochrome P450 2E1 (Cyp2E1) Substrates
Theoretically, bilberry fruit extract might decrease levels of drugs metabolized by CYP2E1.
Animal research shows that exposure to small concentrations of bilberry extract in drinking water for around one month increased CYP2E1 activity by 31%. However, exposure over a 2-month period did not increase CYP2E1 activity. This effect has not been reported in humans.
Erlotinib (Tarceva)
Theoretically, bilberry fruit extract might reduce the efficacy of erlotinib.
In vitro research suggests that bilberry fruit extract and its constituents, delphinidin and delphinidin-3-O-glucoside, inhibit the activity of erlotinib. This interaction has not been reported in humans.
Vitamin C
Alkylating Agents
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin C have on chemotherapy.
Aluminum
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Research in animals and humans shows that vitamin C increases aluminum absorption, theoretically by chelating aluminum and keeping it in solution where it is available for absorption. In people with normal renal function, urinary excretion of aluminum will likely increase, making aluminum retention and toxicity unlikely. Patients with renal failure who take aluminum-containing compounds such as phosphate binders should avoid vitamin C supplements in doses above the recommended dietary allowances.
Antitumor Antibiotics
Theoretically, the antioxidant effects of vitamin C might reduce the effectiveness of antitumor antibiotics.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as doxorubicin. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effects, if any, antioxidants such as vitamin C have on chemotherapy.
Estrogens
Vitamin C might increase blood levels of estrogens.
Increases in plasma estrogen levels of up to 55% occur under some circumstances when vitamin C is taken concurrently with oral contraceptives or hormone replacement therapy, including topical products. It is suggested that vitamin C prevents oxidation of estrogen in the tissues, regenerates oxidized estrogen, and reduces sulfate conjugation of estrogen in the gut wall. When tissue levels of vitamin C are high, these processes are already maximized and supplemental vitamin C does not have any effect on estrogen levels. Increases in plasma estrogen levels may occur when patients who are deficient in vitamin C take supplements. Monitor these patients for estrogen-related side effects.
Fluphenazine (Prolixin)
Theoretically, vitamin C might decrease levels of fluphenazine.
In one patient there was a clinically significant decrease in fluphenazine levels when vitamin C (500 mg twice daily) was started. The mechanism is not known, and there is no further data to confirm this interaction.
Indinavir (Crixivan)
Vitamin C can modestly reduce indinavir levels.
One pharmacokinetic study shows that taking vitamin C 1 gram orally once daily along with indinavir 800 mg orally three times daily reduces the area under the concentration-time curve of indinavir by 14%. The mechanism of this interaction is unknown, but it is unlikely to be clinically significant in most patients. The effect of higher doses of vitamin C on indinavir levels is unknown.
Levothyroxine (Synthroid, Others)
Vitamin C can increase levothyroxine absorption.
Two clinical studies in adults with poorly controlled hypothyroidism show that swallowing levothyroxine with a glass of water containing vitamin C 500-1000 mg in solution reduces thyroid stimulating hormone (TSH) levels and increases thyroxine (T4) levels when compared with taking levothyroxine alone. This suggests that vitamin C increases the oral absorption of levothyroxine, possibly due to a reduction in pH.
Warfarin (Coumadin)
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Vitamin C in high doses may cause diarrhea and possibly reduce warfarin absorption. There are reports of two people who took up to 16 grams daily of vitamin C and had a reduction in prothrombin time. Lower doses of 5-10 grams daily can also reduce warfarin absorption. In many cases, this does not seem to be clinically significant. However, a case of warfarin resistance has been reported for a patient who took vitamin C 500 mg twice daily. Cessation of vitamin C supplementation resulted in a rapid increase in international normalized ratio (INR). Tell patients taking warfarin to avoid taking vitamin C in excessively high doses (greater than 10 grams daily). Lower doses may be safe, but the anticoagulation activity of warfarin should be monitored. Patients who are stabilized on warfarin while taking vitamin C should avoid adjusting vitamin C dosage to prevent the possibility of warfarin resistance.
Acetaminophen (Tylenol, Others)
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
A small pharmacokinetic study in healthy volunteers shows that taking high-dose vitamin C (3 grams) 1.5 hours after taking acetaminophen 1 gram slightly increases the apparent half-life of acetaminophen from around 2.3 hours to 3.1 hours. Ascorbic acid competitively inhibits sulfate conjugation of acetaminophen. However, to compensate, elimination of acetaminophen glucuronide and unconjugated acetaminophen increases. This effect is not likely to be clinically significant.
Aspirin
Acidification of the urine by vitamin C might increase aspirin levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction is not clinically significant.
Choline Magnesium Trisalicylate (Trilisate)
Acidification of the urine by vitamin C might increase choline magnesium trisalicylate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Niacin
Vitamin C might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as vitamin C, or to the combination. It also is not known whether it will occur in other patient populations.
Salsalate (Disalcid)
Acidification of the urine by vitamin C might increase salsalate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams/day vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Coenzyme Q-10
Alkylating Agents
Coenzyme Q10 has antioxidant effects. Theoretically, this may reduce the activity of chemotherapy drugs that generate free radicals.
Theoretically, antioxidants such as coenzyme Q10 might protect tumor cells from chemotherapeutic agents that work by inducing oxidative stress, such as alkylating agents (e.g., cyclophosphamide) and radiation therapy. The clinical importance of this interaction is unknown.
Warfarin (Coumadin)
Coenzyme Q10 is chemically similar to menaquinone and might have vitamin K-like procoagulant effects, which could decrease the effects of warfarin.
Concomitant use of coenzyme Q10 and warfarin might reduce the anticoagulant effects of warfarin. Four cases of decreased warfarin efficacy thought to be due to coenzyme Q10 have been reported. However, there is some preliminary clinical research that suggests coenzyme Q10 might not significantly decrease the effects of warfarin in patients who have a stable INR.
Antihypertensive Drugs
Theoretically, coenzyme Q10 might have additive effects with antihypertensive drugs.
Some clinical research shows that coenzyme Q10 can significantly lower blood pressure, although other studies have shown conflicting results.
Eyebright Aerial Part Extract
Antidiabetes Drugs
Theoretically, eyebright might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Animal research suggests that eyebright lowers blood glucose levels.
Copper
Penicillamine (Cuprimine, Depen)
Theoretically, taking copper with penicillamine might decrease the absorption of penicillamine; separate dosing by at least 2 hours.
Copper chelates penicillamine, which decreases its absorption and may reduce its clinical effects.
Contraceptive Drugs
Theoretically, taking copper with contraceptive drugs might increase the levels and toxic effects of copper.
A meta-analysis of clinical studies suggests that chronic use of oral contraceptives increases serum copper levels by a mean of 57 mcg/dL. In most people, this resulted in levels above the normal reference range for copper.
Brand information
Manufacturer and brand details for EyeCare+, from the product label.
EyeCare+ by Herbs SRA: Common Questions
Does EyeCare+ by Herbs SRA interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Is EyeCare+ safe to take if I'm pregnant?
Can I take EyeCare+ while breastfeeding?
Does EyeCare+ actually help with vision or eye health?
What are the most common side effects?
Is there a risk of bleeding with EyeCare+?
Can EyeCare+ lower my blood sugar?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if EyeCare+ is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind EyeCare+’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin C
Interacts with 207 drugsVitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for immune function, collagen, and acts as an...
Read the full Vitamin C monograph → Herb & supplement monographCopper
Interacts with 31 drugsCopper is an essential trace mineral your body needs in small amounts for making red blood cells, supporting nerves and bones, and helping enzymes work. Most people get enough copper from fo...
Read the full Copper monograph → Herb & supplement monographVitamin E
Interacts with 764 drugsVitamin E is an essential fat-soluble vitamin and antioxidant that most people get in adequate amounts from a normal diet. Supplements can help correct a true deficiency, but high-dose vitam...
Read the full Vitamin E monograph → Herb & supplement monographCoenzyme Q10
Interacts with 198 drugsCoQ10 is a vitamin-like substance your body makes naturally that helps cells produce energy and acts as an antioxidant. It is generally well tolerated and is most studied for heart condition...
Read the full Coenzyme Q10 monograph → Herb & supplement monographBilberry
Interacts with 275 drugsBilberry is a blueberry-like fruit rich in antioxidant plant compounds called anthocyanins, and it has a long history of traditional use for eye health, circulation, and mild diarrhea. While...
Read the full Bilberry monograph → Herb & supplement monographEyebright
Interacts with 86 drugsEyebright is a traditional herb long used for minor eye irritation, redness, and allergy symptoms, but high-quality human studies are very limited. There is not enough reliable evidence to c...
Read the full Eyebright monograph → Herb & supplement monographDocosahexaenoic Acid (dha)
Interacts with 375 drugsDHA is an omega-3 fatty acid found in fatty fish and algae that is a building block for the brain, nervous system, and eyes. It is widely used and generally well tolerated, with the stronges...
Read the full Docosahexaenoic Acid (dha) monograph →Sources & How We Checked
EyeCare+'s label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 233 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Vitamin C 51 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Back DJ, Breckenridge AM, MacIver M, et al. Interaction of ethinyloestradiol with ascorbic acid in man. Br Med J (Clin Res Ed) 1981;282:1516.
- Morris JC, Beeley L, Ballantine N. Interaction of ethinyloestradiol with ascorbic acid in man [letter]. Br Med J (Clin Res Ed) 1981;283:503.
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Dwyer JH, Merz NB, Shirocre AM, et al. Progression of early atherosclerosis and intake of vitamin C and vitamin E from supplements and food. The Los Angeles Atherosclerosis Study. 41st Annual Conference on Cardiovascular Disease Epidemiology and Prevent
- Levine M, Rumsey SC, Daruwala R, et al. Criteria and recommendations for vitamin C intake. JAMA 1999;281:1415-23. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Houston JB, Levy G. Drug biotransformation interactions in man VI: Acetaminophen and ascorbic acid. J Pharm Sci 1976;65:1218-21. PubMed
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Rosenthal G. Interaction of ascorbic acid and warfarin. JAMA 1971;215:1671. DOI
- Hume R, Johnstone JM, Weyers E. Interaction of ascorbic acid and warfarin. JAMA 1972;219:1479. DOI
- Smith EC, Skalski RJ, Johnson GC, Rossi GV. Interaction of ascorbic acid and warfarin. JAMA 1972;221:1166. DOI
- Traxer O, Huet B, Poindexter J, et al. Effect of ascorbic acid consumption on urinary stone risk factors. J Urol 2003;170:397-401.. PubMed
- Domingo JL, Gomez M, Llobet JM, Richart C. Effect of ascorbic acid on gastrointestinal aluminum absorption (letter). Lancet 1991;338:1467.
- Domingo JL, Gomez M, Llobet JM, Corbella J. Influence of some dietary constituents on aluminum absorption and retention in rats. Kidney Int 1991;39:598-601. PubMed
- Partridge NA, Regnier FE, White JL, Hem SL. Influence of dietary constituents on intestinal absorption of aluminum. Kidney Int 1989;35:1413-7. PubMed
- Mc Leod DC, Nahata MC. Inefficacy of ascorbic acid as a urinary acidifier (letter). N Engl J Med 1977;296:1413. DOI
- Hansten PD, Hayton WL. Effect of antacid and ascorbic acid on serum salicylate concentration. J Clin Pharmacol 1980;20:326-31. PubMed
- Dysken MW, Cumming RJ, Channon RA, Davis JM. Drug interaction between ascorbic acid and fluphenazine. JAMA 1979;241:2008. DOI
- Vihtamaki T, Parantainen J, Koivisto AM, et al. Oral ascorbic acid increases plasma oestradiol during postmenopausal hormone replacement therapy. Maturitas 2002;42:129-35. PubMed
- Slain D, Amsden JR, Khakoo RA, et al. Effect of high-dose vitamin C on the steady-state pharmacokinetics of the protease inhibitor indinavir in healthy volunteers. Pharmacotherapy 2005;25:165-70. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Feetam CL, Leach RH, Meynell MJ. Lack of a clinically important interaction between warfarin and ascorbic acid. Toxicol Appl Pharmacol 1975;31:544-7. PubMed
- Weintraub M, Griner PF. Warfarin and ascorbic acid: lack of evidence for a drug interaction. Toxicol Appl Pharmacol 1974;28:53-6. PubMed
- Lee DH, Folsom AR, Harnack L, et al. Does supplemental vitamin C increase cardiovascular disease risk in women with diabetes? Am J Clin Nutr 2004;80:1194-200. PubMed
- Taylor EN, Stampfer MJ, Curhan GC. Dietary factors and the risk of incident kidney stones in men: new insights after 14 years of follow-up. J Am Soc Nephrol 2004;15:3225-32. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Fairweather-Tait S, Hickson K, McGaw B, et al. Orange juice enhances aluminium absorption from antacid preparation. Eur J Clin Nutr. 1994;48(1):71-3.
- Gruenwald, J., Graubaum, H. J., Busch, R., and Bentley, C. Safety and tolerance of ester-C compared with regular ascorbic acid. Adv.Ther. 2006;23(1):171-178.
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Einerson, B., Nathorn, C., Kitiyakara, C., Sirada, M., and Thamlikitkul, V. The efficacy of ascorbic acid in suboptimal responsive anemic hemodialysis patients receiving erythropoietin: a meta-analysis. J Med.Assoc.Thai. 2011;94 Suppl 1:S134-S146.
- Li, G., Li, L., Yu, C., and Chen, L. Effect of vitamins C and E supplementation on Helicobacter pylori eradication: a meta-analysis. Br.J Nutr 2011;106(11):1632-1637.
- Chen X, Shen L, Gu X, et al. High-dose supplementation with vitamin C--induced pediatric urolithiasis: the first case report in a child and literature review. Urology. 2014;84(4):922-4. PubMed
- Sattar A, Willman JE, Kolluri R. Possible warfarin resistance due to interaction with ascorbic acid: case report and literature review. Am J Health Syst Pharm. 2013;70(9):782-6. PubMed
- Yaich S, Chaabouni Y, Charfeddine K, et al. Secondary oxalosis due to excess vitamin C intake: a cause of graft loss in a renal transplant recipient. Saudi J Kidney Dis Transpl. 2014;25(1):113-6. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Rumbold A, Ota E, Nagata C, Shahrook S, Crowther CA. Vitamin C supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004072. PubMed
- Seo MS, Kim JK, Shim JY. High-dose vitamin C promotes regression of multiple pulmonary metastases originating from hepatocellular carcinoma. Yonsei Med J. 2015;56(5):1449-52. PubMed
- Skelin M, Lucijanic T, Amidzic Klaric D, et al. Factors Affecting Gastrointestinal Absorption of Levothyroxine: A Review. Clin Ther. 2017 Feb;39(2):378-403. PubMed
- Jiang K, Tang K, Liu H, Xu H, Ye Z, Chen Z. Ascorbic acid supplements and kidney stones incidence among men and women: a systematic review and meta-analysis. Urol J. 2019;16(2):115-120.
- Thomas S, Patel D, Bittel B, et al. Effect of High-Dose Zinc and Ascorbic Acid Supplementation vs Usual Care on Symptom Length and Reduction Among Ambulatory Patients With SARS-CoV-2 Infection: The COVID A to Z Randomized Clinical Trial. JAMA Netw Open. 2 PubMed
- Giffen MA, McLemore JL. Hyperoxalosis Secondary to Intravenous Vitamin C Administration as a Non-Allopathic Treatment for Cancer. Acad Forensic Pathol 2019;9(1-2):118-126. PubMed
- Maike A, Sturgill D, Gallan A. Oxalate Nephropathy in a Renal Transplant Recipient After Receiving High Dose Ascorbic Acid. Am J Med Sci 2021. PubMed
- Shen ZY, Chen YR, Wang MC, Chang SS. High-dose vitamin C-induced acute oxalate nephropathy in a renal transplant recipient: a case report and literature review. Asian J Surg 2022. PubMed
- Yanase F, Spano S, Maeda A, et al. Mega-dose sodium ascorbate: a pilot, single-dose, physiological effect, double-blind, randomized, controlled trial. Crit Care 2023;27(1):371. PubMed
- Sharma Y, Sumanadasa S, Shahi R, et al. Efficacy and safety of vitamin C supplementation in the treatment of community-acquired pneumonia: a systematic review and meta-analysis with trial sequential analysis. Sci Rep 2024;14(1):11846. PubMed
- Pejcic AV, Petrovic NZ, Djordjic MD, Milosavljevic MN. Vitamin C Levels in Pregnant Women and the Efficacy of Vitamin C Supplements in Preventing Premature Rupture of Membranes: A Systematic Review and Meta-Analysis. Balkan Med J 2024;41(4):248-260. PubMed
Copper 11 references
- Murry JJ, Healy MD. Drug-mineral interactions: a new responsibility for the hospital dietician. J Am Diet Assoc 1991;91:66-73.
- Campbell IA, Elmes PC. Ethambutol and the eye: zinc and copper (letter). Lancet 1975;2:711. DOI
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Kozak SF, Inderlied CB, Hsu HY, et al. The role of copper on ethambutol's antimicrobial action and implications for ethambutol-induced optic neuropathy. Diag Microbiol Infect Dis 1998;30:83-7. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Cantilena LR, Klaassen CD. The effect of chelating agents on the excretion of endogenous metals. Toxicol Appl Pharmacol 1982;63:344-50.
- Babic Z, Tariba B, Kovacic J, Pizent A, Varnai VM, Macan J. Relevance of serum copper elevation induced by oral contraceptives: a meta-analysis. Contraception. 2013 Jun;87(6):790-800. PubMed
- Qui Q, Zhang F, Zhu W, Wu J, Liang M. Copper in diabetes mellitus: a meta-analysis and systematic review of plasma and serum studies. Biol Trace Elem Res 2017;177(1):53-63.
- Walker-Smith PK, Keith DJ, Kennedy CT, Sansom JE. Allergic contact dermatitis caused by copper. Contact Dermatitis 2016;75(3):186-7. PubMed
- Gallentine A. Third-degree burn on the neuropathic lower extremity in a patient with diabetes while wearing a copper-containing compression sock: a case report. Wound Manag Prev 2021;67(12):26-29. DOI
- Chung KJ, Chin YM, Wong MS, Sanmugam A, Singaravel S, Nah SA. Effectiveness of table salt versus copper sulphate in treating umbilical granuloma: A pilot randomized controlled trial. J Pediatr Surg 2022;57(2):261-265. PubMed
Vitamin E 64 references
- Kim JM, White RH. Effect of vitamin E on the anticoagulant response to warfarin. Am J Cardiol 1996;77:545-6. PubMed
- Corrigan JJ Jr. The effect of vitamin E on warfarin-induced vitamin K deficiency. Ann N Y Acad Sci 1982;393:361-8. PubMed
- Corrigan JJ Jr. Coagulation problems relating to vitamin E. Am J Pediatr Hematol Oncol 1979;1:169-73.
- Corrigan JJ Jr, Marcus FI. Coagulopathy associated with vitamin E ingestion. JAMA 1974;230:1300-1. DOI
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Chang T, Benet LZ, Hebert MF. The effect of water-soluble vitamin E on cyclosporine pharmacokinetics in healthy volunteers. Clin Pharmacol Ther 1996;59:297-303. PubMed
- Pan SH, Lopez RR Jr, Sher LS, et al. Enhanced oral cyclosporine absorption with water-soluble vitamin E early after liver transplantation. Pharmacother 1996;16:59-65. DOI
- Anon. Dietary supplementation with n-3 polyunsaturated fatty acids and vitamin E after myocardial infarction: results of the GISSI-Prevenzione trial. Gruppo Italiano per lo Studio della Soprawivenza nell'Infarto miocardico. Lancet 1999;354:447-55. DOI
- Chappell LC, Seed PT, Briley AL, et al. Effect of antioxidants on the occurrence of pre-eclampsia in women at increased risk: a randomised trial. Lancet 1999;354:810-6. DOI
- Yusuf S, Dagenais G, Pogue J, et al. Vitamin E supplementation and cardiovascular events in high-risk patients. The heart outcomes prevention evaluation study investigators. N Engl J Med 2000;342:154-60. PubMed
- Stephens NG, Parsons A, Schofield PM, et al. Randomised controlled trial of vitamin E in patients with coronary disease: Cambridge Heart Antioxidant Study. Lancet 1996;347:781-6.
- The Alpha-Tocopherol, Beta Carotene Cancer Prevention Study Group. The effect of vitamin E and beta carotene on the incidence of lung cancer and other cancers in male smokers. N Engl J Med 1994;330:1029-35. PubMed
- Takahashi O. Haemorrhagic toxicity of a large dose of alpha-, beta-, gamma- and delta-tocopherols, ubiquinone, beta-carotene, retinol acetate and L-ascorbic acid in the rat. Food Chem Toxicol 1995;33:121-8.
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Sano M, Ernesto C, Thomas RG, et al. A controlled trial of selegiline, alpha-tocopherol, or both as treatment for Alzheimer's disease. The Alzheimer's Disease Cooperative Study. N Engl J Med 1997;336:1216-22. PubMed
- Liede KE, Haukka JK, Saxen LM, Heinonen OP. Increased tendency towards gingival bleeding caused by joint effect of alpha-tocopherol supplementation and acetylsalicylic acid. Ann Med 1998;30:542-6.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Liu M, Wallmon A, Olsson-Mortlock C, et al. Mixed tocopherols inhibit platelet aggregation in humans: potential mechanisms. Am J Clin Nutr 2003;77:700-6. PubMed
- Sokol RJ, Johnson KE, Karrer FM, et al. Improvement of cyclosporin absorption in children after liver transplantation by means of water-soluble vitamin E. Lancet 1991;338:212-4.. PubMed
- Stein JH, Carlsson CM, Papcke-Benson K, et al. The effects of lipid-lowering and antioxidant vitamin therapies on flow-mediated vasodilation of the brachial artery in older adults with hypercholesterolemia. J Am Coll Cardiol 2001;38:1806-13.. PubMed
- Carlsson CM, Papcke-Benson K, Carnes M, et al. Health-related quality of life and long-term therapy with pravastatin and tocopherol (vitamin E) in older adults. Drugs Aging 2002;19:793-805. . PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Schrogie JJ. Coagulopathy and fat-soluble vitamins (letter). JAMA 1975;232:19. DOI
- Celestini A, Pulcinelli FM, Pignatelli P, et al. Vitamin E potentiates the antiplatelet activity of aspirin in collagen-stimulated platelets. Haematologica 2002;87:420-6.
- Stampfer MJ, Jakubowski JA, Faigel D, et al. Vitamin E supplementation effect on human platelet function, arachidonic acid metabolism, and plasma prostacyclin levels. Am J Clin Nutr 1988;47:700-6. PubMed
- Jandak J, Steiner M, Richardson PD. Alpha-tocopherol, an effective inhibitor of platelet adhesion. Blood 1989;73:141-9. DOI
- Freedman JE, Farhat JH, Loscalzo J, Keaney JF. Alpha-tocopherol inhibits aggregation of human platelets by a protein kinase C-dependent mechanism. Circulation 1996;94:2434-40. PubMed
- Steiner M. Vitamin E, a modifier of platelet function: rationale and use in cardiovascular and cerebrovascular disease. Nutr Rev 1999;57:306-9. PubMed
- Brodkin RH, Bleiberg J. Sensitivity to topically applied vitamin E. Arch Dermatol 1965;92:76-7. DOI
- Booth SL, Golly I, Sacheck JM, et al. Effect of vitamin E supplementation on vitamin K status in adults with normal coagulation status. Am J Clin Nutr 2004;80:143-8. PubMed
- Miller ER 3rd, Pastor-Barriuso R, Dalal D, et al. Meta-analysis: High-dosage vitamin E supplementation may increase all-cause mortality. Ann Intern Med 2005;142:60520-53. PubMed
- Lonn E, Bosch J, Yusuf S, et al. HOPE and HOPE-TOO Trial Investigators. Effects of long-term vitamin E supplementation on cardiovascular events and cancer: a randomized controlled trial. JAMA 2005;293:1338-47. PubMed
- Landes N, Pfluger P, Kluth D, et al. Vitamin E activates gene expression via the pregnane X receptor. Biochem Pharmacol 2003;65:269-73. . PubMed
- Brigelius-Flohe R. Vitamin E and drug metabolism. Biochem Biophys Res Commun 2003;305:737-40. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Schurks M, Glynn RJ, Rist PM, et al. Effects of vitamin E on stroke subtypes: meta-analysis of randomized controlled trials. BMJ 2010;341: c5702. doi: 10.1136/bmj.c5702.
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Gaziano JM, Glynn RJ, Christen WG, et al. Vitamins E and C in the prevention of prostate total cancer in men: the physicians' health study II randomised controlled trial. JAMA 2009;301:52-62.
- Hayden KM, Welsh-Bohmer KA, Wengreen HJ, et al; Cache County Investigators. Risk of mortality with vitamin E supplements: the Cache County study. Am L Med 2007;120:180-4. PubMed
- Smedts HP, de Vries JH, Rakhshandehroo M, et al. High maternal vitamin E intake by diet or supplements is associated with congenital heart defects in the offspring. BJOG 2009;116:416-23. PubMed
- Klein EA, Thompson IM Jr, Tangen CM, et al. Vitamin E and the risk of prostate cancer: the Selenium and Vitamin E Cancer Prevention Trial (SELECT). JAMA 2011;306:1549-56. PubMed
- Huang, H. Y., Caballero, B., Chang, S., Alberg, A. J., Semba, R. D., Schneyer, C. R., Wilson, R. F., Cheng, T. Y., Vassy, J., Prokopowicz, G., Barnes, G. J., and Bass, E. B. The efficacy and safety of multivitamin and mineral supplement use to prevent ca
- Sesso, H. D., Buring, J. E., Christen, W. G., Kurth, T., Belanger, C., MacFadyen, J., Bubes, V., Manson, J. E., Glynn, R. J., and Gaziano, J. M. Vitamins E and C in the prevention of cardiovascular disease in men: the Physicians' Health Study II randomiz
- Papaioannou, D., Cooper, K. L., Carroll, C., Hind, D., Squires, H., Tappenden, P., and Logan, R. F. Antioxidants in the chemoprevention of colorectal cancer and colorectal adenomas in the general population: a systematic review and meta-analysis. Colorec PubMed
- Cooper, K., Squires, H., Carroll, C., Papaioannou, D., Booth, A., Logan, R. F., Maguire, C., Hind, D., and Tappenden, P. Chemoprevention of colorectal cancer: systematic review and economic evaluation. Health Technol.Assess. 2010;14(32):1-206. PubMed
- Mathew, M. C., Ervin, A. M., Tao, J., and Davis, R. M. Antioxidant vitamin supplementation for preventing and slowing the progression of age-related cataract. Cochrane.Database.Syst.Rev. 2012;6:CD004567. PubMed
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Soares, K. V. and McGrath, J. J. Vitamin E for neuroleptic-induced tardive dyskinesia. Cochrane.Database.Syst.Rev. 2001;(4):CD000209. DOI
- Roed-Petersen, J. and Hjorth, N. Contact dermatitis from antioxidants. Br.J.Dermatol. 1976;94(3):233-241. PubMed
- Brion, L. P., Bell, E. F., Raghuveer, T. S., and Soghier, L. What is the appropriate intravenous dose of vitamin E for very-low-birth-weight infants? J.Perinatol. 2004;24(4):205-207. PubMed
- Manny, T., Pettus, J., Hemal, A., Marks, M., and Mirzazadeh, M. Penile sclerosing lipogranulomas and disfigurement from use of "1Super Extenze" among Laotian immigrants. J.Sex Med. 2011;8(12):3505-3510. PubMed
- Musso, G., Cassader, M., Rosina, F., and Gambino, R. Impact of current treatments on liver disease, glucose metabolism and cardiovascular risk in non-alcoholic fatty liver disease (NAFLD): a systematic review and meta-analysis of randomised trials. Diabe PubMed
- Bell, E. F. Upper limit of vitamin E in infant formulas. J.Nutr. 1989;119(12 Suppl):1829-1831. PubMed
- Manzano, D., Aguirre, A., Gardeazabal, J., Eizaguirre, X., and Diaz Perez, J. L. Allergic contact dermatitis from tocopheryl acetate (vitamin E) and retinol palmitate (vitamin A) in a moisturizing cream. Contact Dermatitis 1994;31(5):324.
- Barak, Y., Swartz, M., Shamir, E., Stein, D., and Weizman, A. Vitamin E (alpha-tocopherol) in the treatment of tardive dyskinesia: a statistical meta-analysis. Ann.Clin.Psychiatry 1998;10(3):101-105.
- Chae CU, Albert CM, Moorthy MV, et al. Vitamin E supplementation and the risk of heart failure in women. Circ Heart Fail. 2012;5(2):176-82. PubMed
- Rumbold A, Ota E, Hori H, Miyazaki C, Crowther CA. Vitamin E supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004069. PubMed
- Prescribing information: KOSELUGO (selumetinib) capsules. U.S. Food and Drug Administration. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2020/213756s000lbl.pdf.
- Warshaw EM, Ruggiero JL, DeKoven JG, et al. Patch testing with tocopherol and tocopherol acetate: the North American Contact Dermatitis Group experience, 2001 to 2016. Dermatitis. 2021;32(5):308-18. PubMed
- US Preventive Services Task Force, Mangione CM, Barry MJ, et al. Vitamin, Mineral, and Multivitamin Supplementation to Prevent Cardiovascular Disease and Cancer: US Preventive Services Task Force Recommendation Statement. JAMA 2022;327(23):2326-2333. PubMed
- Abrol R, Kaushik R, Goel D, Sama S, Kaushik RM, Kala M. Vitamin E-induced coagulopathy in a young patient: a case report. J Med Case Rep 2023;17(1):107. PubMed
- Abtahi-Naeini B, Rastegarnasab F, Saffaei A. Liquid vitamin E injection for cosmetic facial rejuvenation: A disaster report of lipogranuloma. J Cosmet Dermatol 2022;21(11):5549-5554. PubMed
Coenzyme Q10 40 references
- Kamikawa T, Kobayashi A, Yamashita T, et al. Effects of coenzyme Q10 on exercise tolerance in chronic stable angina pectoris. Am J Cardiol 1985;56:247-51. PubMed
- Langsjoen P, Willis R, Folkers K. Treatment of essential hypertension with coenzyme Q10. Mol Aspects Med 1994;S265-72. PubMed
- Spigset O. Reduced effect of warfarin caused by ubidecarenone. Lancet 1994;334:1372-3. PubMed
- Singh RB, Niaz MA, Rastogi SS, et al. Effect of hydrosoluble coenzyme Q10 on blood pressures and insulin resistance in hypertensive patients with coronary artery disease. J Hum Hypertens 1999;13:203-8. PubMed
- Portakal O, Ozkaya O, Erden Inal M, et al. Coenzyme Q10 concentrations and antioxidant status in tissues of breast cancer patients. Clin Biochem 2000;33:279-84. PubMed
- Lund EL, Quistorff B, Spang-Thomsen M, Kristjansen PE. Effect of radiation therapy on small-cell lung cancer is reduced by ubiquinone intake. Folia Microbiol (Praha) 1998;43:505-6. PubMed
- Langsjoen PH, Langsjoen PH, Folkers K. Long-term efficacy and safety of coenzyme Q10 therapy for idiopathic dilated cardiomyopathy. Am J Cardiol 1990;65:521-3. PubMed
- Heck AM, DeWitt BA, Lukes AL. Potential interactions between alternative therapies and warfarin. Am J Health Syst Pharm 2000;57:1221-7. DOI
- Landbo C, Almdal TP. [Interaction between warfarin and coenzyme Q10]. Ugeskr Laeger 1998;160:3226-7.
- Baggio E, Gandini R, Plauncher AC, et al. Italian multicenter study on the safety and efficacy of coenzyme Q10 as adjunctive therapy in heart failure. CoQ10 Drug Surveillance Investigators. Mol Aspects Med 1994;15 Suppl:S287-94. PubMed
- Burke BE, Neuenschwander R, Olson RD. Randomized, double-blind, placebo-controlled trial of coenzyme Q10 in isolated systolic hypertension. South Med J 2001;94:1112-7. PubMed
- The Huntington Study Group. A randomized, placebo-controlled trial of coenzyme Q10 and remacemide in Huntington's disease. Neurology 2001;57:397-404.
- Hodgson JM, Watts GF, Playford DA, et al. Coenzyme Q10 improves blood pressure and glycaemic control: a controlled trial in subjects with type 2 diabetes. Eur J Clin Nutr 2002;56:1137-42. PubMed
- Singh RB, Neki NS, Kartikey K, et al. Effect of coenzyme Q10 on risk of atherosclerosis in patients with recent myocardial infarction. Mol Cell Biochem 2003;246:75-82. DOI
- Porterfield LM. Why did the response to warfarin change? RN 2000;63:107.
- Sandor PS, Di Clemente L, Coppola G, et al. Efficacy of coenzyme Q10 in migraine prophylaxis: A randomized controlled trial. Neurology 2005;64:713-5. PubMed
- Engelsen J, Nielsen JD, Winther K. Effect of coenzyme Q10 and Ginkgo biloba on warfarin dosage in stable, long-term warfarin treated outpatients. A randomised, double blind, placebo-crossover trial. Thromb Haemost 2002;87:1075-6. DOI
- Berman M, Erman A, Ben-Gal T, et al. Coenzyme Q10 in patients with end-stage heart failure awaiting cardiac transplantation: a randomized, placebo-controlled study. Clin Cardiol 2004;27:295–9. PubMed
- Storch A, Jost WH, Vieregge P, et al. Randomized, double-blind, placebo-controlled trial on symptomatic effects of coenzyme Q10 in Parkinson disease. Arch Neurol 2007;64:938-44. DOI
- Digiesi V, Cantini F, Oradei A, et al. Coenzyme Q10 in essential hypertension. Mol Aspects Med 1994;15 Suppl:s257-63. PubMed
- Yamagami T, Takagi M, Akagami H, et al. Effect of coenzyme Q10 on essential hypertension, a double blind controlled study. In: Folkers KA, Yamamura Y, eds. Biomedical and Clinical Aspects of Coenzyme Q, Vol. 5. Amsterdam: Elsevier Science Publications, 19
- Ho MJ, Bellusci A, Wright JM. Blood pressure lowering efficacy of coenzyme Q10 for primary hypertension (review). Cochrane Database Syst Rev 2009;(4):CD007435. PubMed
- Rosenfeldt, F. L., Haas, S. J., Krum, H., Hadj, A., Ng, K., Leong, J. Y., and Watts, G. F. Coenzyme Q10 in the treatment of hypertension: a meta-analysis of the clinical trials. J Hum.Hypertens. 2007;21(4):297-306. PubMed
- Stamelou, M., Reuss, A., Pilatus, U., Magerkurth, J., Niklowitz, P., Eggert, K. M., Krisp, A., Menke, T., Schade-Brittinger, C., Oertel, W. H., and Hoglinger, G. U. Short-term effects of coenzyme Q10 in progressive supranuclear palsy: a randomized, place DOI
- Keogh A, Fenton S, Leslie C, et al. Randomised double-blind, placebo-controlled trial of coenzyme Q, therapy in class II and III systolic heart failure. Heart Lung Circ. 2003;12:135-41.
- Gane, E. J., Weilert, F., Orr, D. W., Keogh, G. F., Gibson, M., Lockhart, M. M., Frampton, C. M., Taylor, K. M., Smith, R. A., and Murphy, M. P. The mitochondria-targeted anti-oxidant mitoquinone decreases liver damage in a phase II study of hepatitis C
- Lynch, D. R., Perlman, S. L., and Meier, T. A phase 3, double-blind, placebo-controlled trial of idebenone in friedreich ataxia. Arch Neurol. 2010;67(8):941-947. PubMed
- Young, J. M., Florkowski, C. M., Molyneux, S. L., McEwan, R. G., Frampton, C. M., Nicholls, M. G., Scott, R. S., and George, P. M. A randomized, double-blind, placebo-controlled crossover study of coenzyme Q10 therapy in hypertensive patients with the me
- Ishiyama, T., Morita, Y., Toyama, S., Yamagami, T., and Tsukamoto, N. A clinical study of the effect of coenzyme Q on congestive heart failure. Jpn.Heart J 1976;17(1):32-42. PubMed
- Matthews, P. M., Ford, B., Dandurand, R. J., Eidelman, D. H., O'Connor, D., Sherwin, A., Karpati, G., Andermann, F., and Arnold, D. L. Coenzyme Q10 with multiple vitamins is generally ineffective in treatment of mitochondrial disease. Neurology 1993;43(5
- Malm, C., Svensson, M., Sjoberg, B., Ekblom, B., and Sjodin, B. Supplementation with ubiquinone-10 causes cellular damage during intense exercise. Acta Physiol Scand. 1996;157(4):511-512. PubMed
- Singh, R. B., Wander, G. S., Rastogi, A., Shukla, P. K., Mittal, A., Sharma, J. P., Mehrotra, S. K., Kapoor, R., and Chopra, R. K. Randomized, double-blind placebo-controlled trial of coenzyme Q10 in patients with acute myocardial infarction. Cardiovasc. PubMed
- Digiesi V, Cantini F, and Brodbeck B. Effect of coenzyme Q10 on essential arterial hypertension. Current Therapeutic Research 1990;47(5):841-845.
- Parkinson Study Group QE3 Investigators, Beal MF, Oakes D, et al. A randomized clinical trial of high-dosage coenzyme Q10 in early Parkinson disease: no evidence of benefit. JAMA Neurol. 2014;71(5):543-52.
- Alehagen U, Johansson P, Bjornstedt M, et al. Cardiovascular mortality and N-terminal-proBNP reduced after combined selenium and coenzyme Q10 supplementation: A 5-year prospective randomized double-blind placebo-controlled trial among elderly Swedish citi
- Ho MJ, Li EC, Wright JM. Blood pressure lowering efficacy of coenzyme Q10 for primary hypertension. Cochrane Database Syst Rev. 2016 Mar 3;3:CD007435. doi: 10.1002/14651858.CD007435.pub3. PubMed
- Tabrizi R, Akbari M, Sharifi N, Lankarani KB, Moosazadeh M, Kolahdooz F, et al. The effects of coenzyme Q10 supplementation on blood pressures among patients with metabolic diseases: a systematic review and meta-analysis of randomized controlled trials. PubMed
- Tsai IC, Hsu CW, Chang CH, Tseng PT, Chang KV. Effectiveness of coenzyme Q10 supplementation for reducing fatigue: A systematic review and meta-analysis of randomized controlled trials. Front Pharmacol 2022;13:883251. PubMed
- Yaghini O, Hoseini N, Ghazavi MR, et al. A comparative study on the efficacy of coenzyme Q10 and amitriptyline in the prophylactic treatment of migraine headaches in children: A randomized controlled trial. Adv Biomed Res 2022;11:43. PubMed
- Hansen KS, Mogensen TH, Agergaard J, et al. High-dose coenzyme Q10 therapy versus placebo in patients with post COVID-19 condition: A randomized, phase 2, crossover trial. Lancet Reg Health Eur 2022. PubMed
Bilberry 14 references
- Cignarella A, Nastasi M, Cavalli E, Puglisi L. Novel lipid-lowering properties of Vaccinium myrtillus L. leaves, a traditional antidiabetic treatment, in several models of rat dyslipidaemia: a comparison with ciprofibrate. Thromb Res 1996;84:311-22. PubMed
- Morazzoni P, Magistretti MJ. Activity of Myrtocyan, an anthosyanoside complex from Vaccinium myrtillus (VMA), on platelet aggregation and adhesiveness. Fitoterapia 1990;61:13-21.
- Erlund, I., Koli, R., Alfthan, G., Marniemi, J., Puukka, P., Mustonen, P., Mattila, P., and Jula, A. Favorable effects of berry consumption on platelet function, blood pressure, and HDL cholesterol. Am J Clin Nutr 2008;87(2):323-331. PubMed
- Hawrelak, J. A. and Myers, S. P. Effects of two natural medicine formulations on irritable bowel syndrome symptoms: a pilot study. J Altern Complement Med 2010;16(10):1065-1071. PubMed
- Morazzoni P and Magistretti MJ. Effects of Vaccinium myrtillus anthocyanosides on prostacyclin-like activity in rat arterial issue. Fitoterapia 1986;57:11-14.
- Pulliero G, Montin S, Bettini V, and et al. Ex vivo study of the inhibitory effects of Vaccinium myrtillus anthocyanosides on human platelet aggregation. Fitoterapia 1989;60:69-75.
- Bottecchia D. Preliminary report on the inhibitory effect of vaccinium myrtillus anthocyanosides on platelet aggregation and clot retraction. Fitoterapia 1987;48:3-8.
- Fdez, M., Zaragoza, F., and Alvarez, P. In vitro platelet aggregation effects of anthocyanosides of vaccinium myrtilus L. Anales de la Real Academia de Farmacia 1983;49:79-90.
- Biedermann L, Mwinyi J, Scharl M, Frei P, Zeitz J, Kullak-Ublick GA, et al. Bilberry ingestion improves disease activity in mild to moderate ulcerative colitis-an open pilot study. 2013 May;7(4):271-9. PubMed
- Hoggard N, Cruickshank M, Moar KM, Bestwick C, Holst J, Russell W, et al. A single supplement of a standardized bilberry (Vaccinium myrtillus L.) extract (36% wet weight anthocyanins) modifies glycaemic response in individuals with type 2 diabetes control
- Aichinger G, Pahlke G, Nagel LJ, Berger W, Marko D. Bilberry extract, its major phenolic compounds, and soy isoflavone genistein antagonize the cytostatic drug erlotinib in human epithelial cells. Food Funct 2016;7(8):3628-36.
- Prokop J, Lněničková K, Cibicek N, et al. Effect of bilberry extract (Vaccinium myrtillus L.) on drug-metabolizing enzymes in rats. Food Chem Toxicol 2019;129:382-90. PubMed
- Chan SW, Chu TTW, Choi SW, Benzie IFF, Tomlinson B. Impact of short-term bilberry supplementation on glycemic control, cardiovascular disease risk factors, and antioxidant status in Chinese patients with type 2 diabetes. Phytother Res 2021. Online ahead o PubMed
- Bøhn SK, Myhrstad MCW, Thoresen M, et al. Bilberry/red grape juice decreases plasma biomarkers of inflammation and tissue damage in aged men with subjective memory impairment -a randomized clinical trial. BMC Nutr 2021;7(1):75. PubMed
Eyebright 4 references
- Newall CA, Anderson LA, Philpson JD. Herbal Medicine: A Guide for Healthcare Professionals. London, UK: The Pharmaceutical Press, 1996.
- Wichtl MW. Herbal Drugs and Phytopharmaceuticals. Ed. N.M. Bisset. Stuttgart: Medpharm GmbH Scientific Publishers, 1994.
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- Porchezhian, E., Ansari, S. H., and Shreedharan, N. K. Antihyperglycemic activity of Euphrasia officinale leaves. Fitoterapia 2000;71(5):522-526. PubMed
Docosahexaenoic Acid (dha) 49 references
- Akedo I, Ishikawa H, Nakamura T, et al. Three cases with familial adenomatous polyposis diagnosed as having malignant lesions in the course of a long-term trial using docosahexanoic acid (DHA)-concentrated fish oil capsules (abstract). Jpn J Clin Oncol PubMed
- Prisco D, Paniccia R, Bandinelli B, et al. Effect of medium-term supplementation with a moderate dose of n-3 polyunsaturated fatty acids on blood pressure in mild hypertensive patients. Thromb Res 1998;1:105-12.
- Grimsgaard S, Bonaa KH, Hansen JB, Nordoy A. Highly purified eicosapentaenoic acid and docosahexaenoic acid in humans have similar triacylglycerol-lowering effects but divergent effects on serum fatty acids. Am J Clin Nutr 1997;66:649-59.
- Toft I, Bonaa KH, Ingebretsen OC, et al. Effects of n-3 polyunsaturated fatty acids on glucose homeostasis and blood pressure in essential hypertension. A randomized, controlled trial. Ann Intern Med 1995;123:911-8.
- Sacks FM, Hebert P, Appel LJ, et al. Short report: the effect of fish oil on blood pressure and high-density lipoprotein-cholesterol levels in phase I of the trials of hypertension prevention. J Hypertens 1994;12:209-13.
- Vandongen R, Mori TA, Burke V, et al. Effects on blood pressure of omega 3 fats in subjects at increased risk of cardiovascular disease. Hypertension 1993;22:371-9. PubMed
- FDA. Center for Food Safety and Applied Nutrition. Letter regarding dietary supplement health claim for omega-3 fatty acids and coronary heart disease. Available at: http://www.fda.gov/ohrms/dockets/dockets/95s0316/95s-0316-Rpt0272-38-Appendix-D-Reference
- Pedersen HS, Mulvad G, Seidelin KN, et al. N-3 fatty acids as a risk factor for haemorrhagic stroke. Lancet 1999;353:812-3. PubMed
- Ito Y, Suzuki K, Imai H, et al. Effects of polyunsaturated fatty acids on atrophic gastritis in a Japanese population. Cancer Lett 2001;163:171-8. PubMed
- Kris-Ehterton PM, Harris WS, Appel LJ, et al. Fish consumption, fish oil, omega-3 fatty acids, and cardiovascular disease. Circulation 2002;106:2747-57. PubMed
- Woodman RJ, Mori TA, Burke V, et al. Effects of purified eicosapentaenoic and docosahexaenoic acids on glycemic control, blood pressure, and serum lipids in type 2 diabetic patients with treated hypertension. Am J Clin Nutr 2002;76:1007-15.. PubMed
- Marangell LB, Martinez JM, Zboyan HA, et al. A double-blind, placebo-controlled study of the omega-3 fatty acid docosahexaenoic acid in the treatment of major depression. Am J Psychiatry 2003;160:996-8.. PubMed
- Leng GC, Smith FB, Fowkes FG, et al. Relationship between plasma essential fatty acids and smoking, serum lipids, blood pressure and haemostatic and rheological factors. Prostaglandins Leukot Essent Fatty Acids 1994;51:101-8. PubMed
- Nelson GJ, Schmidt PS, Bartolini GL, et al. The effect of dietary docosahexaenoic acid on platelet function, platelet fatty acid composition, and blood coagulation in humans. Lipids 1997;32:1129-36. PubMed
- Wheaton DH, Hoffman DR, Locke KG, et al. Biological safety assessment of docosahexaenoic acid supplementation in a randomized clinical trial for X-linked retinitis pigmentosa. Arch Ophthalmol 2003;121:1269-78. PubMed
- Malcolm CA, McCulloch DL, Montgomery C, et al. Maternal docosahexaenoic acid supplementation during pregnancy and visual evoked potential development in term infants: a double blind, prospective, randomised trial. Arch Dis Child Fetal Neonatal Ed 2003;88: DOI
- Sanjurjo P, Ruiz-Sanz JI, Jimeno P, et al. Supplementation with docosahexaenoic acid in the last trimester of pregnancy: maternal-fetal biochemical findings. J Perinat Med 2004;32:132-6.
- Montgomery C, Speake BK, Cameron A, et al. Maternal docosahexaenoic acid supplementation and fetal accretion. Br J Nutr 2003;90:135-45. DOI
- Lauritzen L, Hoppe C, Straarup EM, Michaelsen KF. Maternal fish oil supplementation in lactation and growth during the first 2.5 years of life. Pediatr Res 2005;58:235-42. PubMed
- Hawkes JS, Bryan DL, Makrides M, et al. A randomized trial of supplementation with docosahexaenoic acid-rich tuna oil and its effects on the human milk cytokines interleukin 1 beta, interleukin 6, and tumor necrosis factor alpha. Am J Clin Nutr 2002;75:75
- Uauy R, Hoffman DR, Mena P, et al. Term infant studies of DHA and ARA supplementation on neurodevelopment: Results of randomized controlled trials. J Pediatr 2003;143:S17-25. PubMed
- Decsi, T., Campoy, C., and Koletzko, B. Effect of N-3 polyunsaturated fatty acid supplementation in pregnancy: the Nuheal trial. Adv.Exp Med Biol 2005;569:109-113. PubMed
- Mori, T. A., Bao, D. Q., Burke, V., Puddey, I. B., and Beilin, L. J. Docosahexaenoic acid but not eicosapentaenoic acid lowers ambulatory blood pressure and heart rate in humans. Hypertension 1999;34(2):253-260. PubMed
- Otto, S. J., van Houwelingen, A. C., and Hornstra, G. The effect of supplementation with docosahexaenoic and arachidonic acid derived from single cell oils on plasma and erythrocyte fatty acids of pregnant women in the second trimester. Prostaglandins Le PubMed
- Helland, I. B., Saugstad, O. D., Smith, L., Saarem, K., Solvoll, K., Ganes, T., and Drevon, C. A. Similar effects on infants of n-3 and n-6 fatty acids supplementation to pregnant and lactating women. Pediatrics 2001;108(5):E82. PubMed
- Nestel, P., Shige, H., Pomeroy, S., Cehun, M., Abbey, M., and Raederstorff, D. The n-3 fatty acids eicosapentaenoic acid and docosahexaenoic acid increase systemic arterial compliance in humans. Am.J.Clin.Nutr. 2002;76(2):326-330. PubMed
- Woodman, R. J., Mori, T. A., Burke, V., Puddey, I. B., Barden, A., Watts, G. F., and Beilin, L. J. Effects of purified eicosapentaenoic acid and docosahexaenoic acid on platelet, fibrinolytic and vascular function in hypertensive type 2 diabetic patients PubMed
- Jensen, C. L., Voigt, R. G., Prager, T. C., Zou, Y. L., Fraley, J. K., Rozelle, J. C., Turcich, M. R., Llorente, A. M., Anderson, R. E., and Heird, W. C. Effects of maternal docosahexaenoic acid intake on visual function and neurodevelopment in breastfed
- Theobald, H. E., Goodall, A. H., Sattar, N., Talbot, D. C., Chowienczyk, P. J., and Sanders, T. A. Low-dose docosahexaenoic acid lowers diastolic blood pressure in middle-aged men and women. J Nutr 2007;137(4):973-978.
- Mischoulon D, Best-Popescu C, Laposata M, et al. A double-blind dose-finding pilot study of docosahexaenoic acid (DHA) for major depressive disorder. Eur Neuropsychopharmacol. 2008;18(9):639-645. PubMed
- Birch EE, Carlson SE, Hoffman DR, et al. The DIAMOND (DHA Intake And Measurement Of Neural Development) Study: a double-masked, randomized controlled clinical trial of the maturation of infant visual acuity as a function of the dietary level of docosahexa
- Carlson SE, Colombo J, Gajewski BJ, Gustafson KM, Mundy D, Yeast J, Georgieff MK, Markley LA, Kerling EH, Shaddy DJ. DHA supplementation and pregnancy outcomes. Am J Clin Nutr. 2013 Apr;97(4):808-15. PubMed
- Escamilla-Nuñez MC, Barraza-Villarreal A, Hernández-Cadena L, Navarro-Olivos E, Sly PD, Romieu I. Omega-3 fatty acid supplementation during pregnancy and respiratory symptoms in children. Chest. 2014 Aug;146(2):373-82. PubMed
- Fu YQ, Zheng JS, Yang B, Li D. Effect of individual omega-3 fatty acids on the risk of prostate cancer: a systematic review and dose-response meta-analysis of prospective cohort studies. J Epidemiol. 2015;25(4):261-74. PubMed
- Imhoff-Kunsch B, Stein AD, Villalpando S, Martorell R, Ramakrishnan U. Docosahexaenoic acid supplementation from mid-pregnancy to parturition influenced breast milk fatty acid concentrations at 1 month postpartum in Mexican women. J Nutr. 2011 Feb;141(2): PubMed
- Judge MP, Cong X, Harel O, Courville AB, Lammi-Keefe CJ. Maternal consumption of a DHA-containing functional food benefits infant sleep patterning: an early neurodevelopmental measure. Early Hum Dev. 2012 Jul;88(7):531-7. PubMed
- Mulder KA, King DJ, Innis SM. Omega-3 fatty acid deficiency in infants before birth identified using a randomized trial of maternal DHA supplementation in pregnancy. PLoS One. 2014 Jan 10;9(1):e83764. PubMed
- Richardson AJ, Burton JR, Sewell RP, Spreckelsen TF, Montgomery P. Docosahexaenoic acid for reading, cognition and behavior in children aged 7-9 years: a randomized, controlled trial (the DOLAB Study). PLoS One. 2012;7(9):e43909. PubMed
- Drugs in Pregnancy and Lactation 2012;25(4);3-4
- FDA announces qualified health claims for omega-3 fatty acids. Available at: https://www.fda.gov/Food/LabelingNutrition/ucm072756.htm. Accessed April 15 2019.
- Breastfeeding and the use of human milk. Section on Breastfeeding. Pediatrics. 2012;129(3):e827-41. PubMed
- Zhang Z, Fulgoni VL, Kris-Etherton PM, Mitmesser SH. Dietary Intakes of EPA and DHA Omega-3 Fatty Acids among US Childbearing-Age and Pregnant Women: An Analysis of NHANES 2001-2014. Nutrients. 2018;10(4). PubMed
- Montgomery P, Spreckelsen TF, Burton A, Burton JR, Richardson AJ. Docosahexaenoic acid for reading, working memory and behavior in UK children aged 7-9: A randomized controlled trial for replication (the DOLAB II study). PLoS One. 2018;13(2):e0192909. PubMed
- Marc I, Piedboeuf B, Lacaze-Masmonteil T, et al. Effect of maternal docosahexaenoic acid supplementation on bronchopulmonary dysplasia-free survival in breastfed preterm infants: A randomized clinical trial. JAMA. 2020;324(2):157-167. PubMed
- Fougère H, Bilodeau JF, Lavoie PM, et al. Docosahexaenoic acid-rich algae oil supplementation on breast milk fatty acid profile of mothers who delivered prematurely: a randomized clinical trial. Sci Rep 2021;11(1):21492. PubMed
- Garmendia ML, Casanello P, Flores M, Kusanovic JP, Uauy R. The effects of a combined intervention (docosahexaenoic acid supplementation and home-based dietary counseling) on metabolic control in obese and overweight pregnant women: the MIGHT study. Am J O PubMed
- Christifano DN, Gustafson KM, Carlson SE, et al. Maternal docosahexaenoic acid exposure needed to achieve maternal-newborn EQ. Nutrients 2022;14(16):3300. PubMed
- Vizzari G, Morniroli D, Alessandretti F, et al. Comparative analysis of docosahexaenoic acid (DHA) content in mother's milk of term and preterm mothers. Nutrients 2022;14(21):4595. PubMed
- Yang Y, Li G, Li F, et al. Impact of DHA from algal oil on the breast milk DHA levels of lactating women: A randomized controlled trial in China. Nutrients 2022;14(16):3410. PubMed
See these in context on the Docosahexaenoic Acid (dha) monograph →
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC