
For Daytime Ingredients & Drug Interactions
by Stasis
What is this page for?
First and foremost: checking For Daytime against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
For Daytime is a dietary supplement by Stasis with 9 active ingredients. Its ingredients are commonly taken for morning sickness in pregnancy, premenstrual syndrome (pms), preventing or treating b6 deficiency.Based on those ingredients, 1,672 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Shoden, Sage Extract, Green Tea Extract, Decaffeinated. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against For Daytime by Stasis
Ask about any prescription or over-the-counter medication and we check it for interactions with For Daytime by Stasis — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of For Daytime by Stasis
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
For Daytime contains nine active ingredients. Vitamin B6 and vitamin B12 are B-complex vitamins that support energy metabolism and nerve function.
L-theanine is an amino acid from tea that may support calm focus without drowsiness. Selenium is a mineral with antioxidant roles.
Affron is a standardized saffron extract studied for mood and cognitive effects. Green tea extract (decaffeinated) provides polyphenol antioxidants.
Shoden is a standardized ashwagandha extract traditionally used for stress and sleep. Sage extract offers plant compounds historically linked to memory and hot-flash relief.
The product also contains inactive ingredients — microcrystalline cellulose, magnesium stearate, and cellulose — which are fillers and binders.
Does it work?
Moderate evidence
The evidence for this product's ingredients is mixed. Vitamin B6 is effective for sideroblastic anemia and B6 deficiency, and likely effective for high homocysteine levels; it's possibly effective for pregnancy-related nausea.
Vitamin B12 is effective for B12 deficiency. L-theanine is possibly effective for cognitive function, but evidence is insufficient for age-related cognitive decline and Alzheimer's disease.
Selenium is likely effective for selenium deficiency and possibly effective for pre-eclampsia, but possibly ineffective for high cholesterol. Green tea extract is likely effective for human papillomavirus (HPV) and possibly effective for ovarian cancer and high cholesterol.
Affron (saffron) is possibly effective for chemotherapy-related nerve pain and Alzheimer's disease. Ashwagandha is possibly effective for insomnia, anxiety, stress, and generalized anxiety disorder.
Sage extract is possibly effective for menopausal symptoms, high cholesterol, and cognitive function, but possibly ineffective for post-operative pain.
How safe is it?
Well-documented data
Most ingredients are generally well tolerated at standard doses. Vitamin B6 is safe in normal amounts but high doses over time can cause nerve damage (a rare serious effect at very high intakes).
Vitamin B12 is considered very safe with no established upper limit. L-theanine is generally well tolerated short-term in healthy adults, though long-term safety is not well studied; it may cause headaches or drowsiness.
Selenium is safe within recommended amounts but excess can be toxic, causing nail and hair loss, nausea, and in extreme cases, organ failure. Saffron is likely safe at food amounts but medicinal doses can carry risk; it may cause nausea, vomiting, and rarely anaphylaxis.
Green tea extract is well tolerated but concentrated high-dose forms have rarely caused liver injury. Ashwagandha is generally well tolerated short-term but has been linked to rare cases of liver problems; it is traditionally avoided in pregnancy due to concerns about miscarriage, and not enough safety data exists for breastfeeding.
Sage is safe as food or short-term tea but concentrated extracts should be used cautiously. We hold no safety data for Oceanix.
Meds to double-check
Major interaction found
Check this product against blood-pressure medications, cholesterol drugs (especially atorvastatin), beta-blockers (especially nadolol), blood thinners (especially warfarin), diabetes medications, seizure medications (phenytoin, phenobarbital, valproate, ethosuximide, felbamate), thyroid hormone, and sedatives or anxiety medications before you start. The caffeine in green tea can also interact with ephedrine and may interfere with stress-test drugs like dipyridamole.
If you're not sure whether your medications are affected, run them through the checker below.
The bottom line
Scorecard at a glanceFully disclosed formula with some supporting evidence for its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
This is a daytime blend aimed at focus, mood, and stress — useful if you're looking for those effects without the jitters. However, if you take blood-pressure medication, blood thinners, diabetes drugs, seizure medications, thyroid hormone, or cholesterol medication, you need to check this product's ingredients against your exact drugs before starting.
Talk to your pharmacist or doctor first, especially if you're pregnant, breastfeeding, or on multiple medications.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 8 of 9 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jan 23, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about For Daytime, straight from the product label.
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
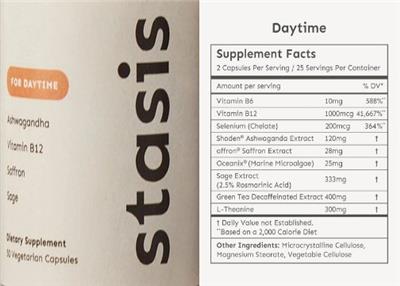
Supplement Facts
The label details for For Daytime by Stasis, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Vitamin B6 | 10 mg | 588% |
| Vitamin B12 | 1000 mcg | 41667% |
| L-Theanine | 300 mg | -- |
| Selenium | 200 mcg | 364% |
| Affron | 28 mg | -- |
| Green Tea Extract, Decaffeinated | 400 mg | -- |
| Shoden | 120 mg | -- |
| Oceanix | 25 mg | -- |
| Sage Extract | 333 mg | -- |
Other ingredients: Microcrystalline Cellulose, Magnesium Stearate, Cellulose
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formula
Ashwaganda Vitamin B12 Saffron Sage
FDA Statement of Identity
Dietary Supplement
Suggested/Recommended/Usage/Directions
Daytime
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
For Daytime by Stasis label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in For Daytime by Stasis
These are the 9 active ingredients this product is made of. Select any to open its full monograph.
Serving size2 Capsule(s) Dosage formCapsule Servings per container25 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Vitamin B6
Interacts with210 drugs
Vitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is b...
Vitamin B6 monograph & interactionsVitamin B12
Interacts with20 drugs
Vitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very h...
Vitamin B12 monograph & interactionsL-Theanine
Interacts with565 drugs
Theanine (usually L-theanine) is an amino acid found naturally in tea leaves that many people take to feel calmer and less stressed without strong dro...
L-Theanine monograph & interactionsSelenium
Interacts with321 drugs
Selenium is an essential trace mineral your body needs in small amounts for thyroid function, antioxidant defense, and immune health. Most people who...
Selenium monograph & interactionsAffron
Interacts with521 drugs
Saffron is a costly spice that has shown promise in early studies for mild-to-moderate depression and some mood and PMS symptoms, but most research us...
Affron monograph & interactionsGreen Tea Extract, Decaffeinated
Interacts with1,293 drugs
Green tea is a popular beverage rich in antioxidants called catechins, and drinking it in normal amounts is considered safe for most people. Concentra...
Green Tea Extract, Decaffeinated monograph & interactionsShoden
Interacts with1,372 drugs
Ashwagandha is an Ayurvedic herb most often taken to help with stress, anxiety, and sleep, and some small studies suggest it may help, though the evid...
Shoden monograph & interactionsOceanix
Sage Extract
Interacts with1,296 drugs
Sage is a common kitchen herb that is generally safe in food amounts and is traditionally used for sore throats, digestion, sweating, and memory. Some...
Sage Extract monograph & interactionsOther (inactive) ingredients: Microcrystalline Cellulose, Magnesium Stearate, Cellulose. These complete the product’s ingredient list but are not active constituents.
For Daytime by Stasis Drug Interactions
HelloPharmacist Interaction Report
Stasis For Daytime contains nine ingredients, several of which interact with medications.
The most serious interactions involve green tea extract, which significantly reduces the levels of two important drugs: nadolol (a beta-blocker for heart rhythm and blood pressure) and atorvastatin (a cholesterol medication). Both interactions are Major severity — green tea can decrease nadolol levels by roughly 85% and atorvastatin levels by about 24%, potentially making these drugs much less effective.
Read the full breakdown — every affected drug type, severity by severity
Several ingredients pose Moderate-severity risks. Vitamin B6 may add to the blood-pressure-lowering effect of antihypertensive drugs, and high doses can reduce the effectiveness of seizure medications (phenobarbital and phenytoin).
L-theanine and saffron (Affron) can also lower blood pressure and may have additive effects with blood-pressure medications. Saffron additionally interacts with diabetes medications (increasing low-blood-sugar risk) and with caffeine (potentially raising caffeine levels).
Ashwagandha carries multiple Moderate interactions: it may worsen low blood sugar with diabetes drugs, lower blood pressure further, interfere with thyroid hormone therapy, and theoretically increase sedation with sleep aids and anxiety medications. Selenium may increase bleeding risk with blood thinners like warfarin, and sage extract can inhibit liver enzymes that break down many common medications, potentially raising their levels.
Vitamin B12 has a Minor interaction with metformin (diabetes), which may lower B12 levels over time. Green tea also theoretically poses Minor risks with seizure medications and brain depressants.
Altogether, these interactions span 1,649 individual medications. We could not check Oceanix — we hold no data for it.
Check your exact medications with the search tool on this page.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against For Daytime?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in For Daytime interact with 1,672 drugs. Click any drug to see the details.
8 of the 9 ingredients in For Daytime interact with drugs. Each result below shows which ingredient is responsible. Shoden Sage Extract Green Tea Extract, Decaffeinated L-Theanine Affron Selenium Vitamin B6 Vitamin B12
Aminophylline, Amobarbital, EphedrineAmesec
How Aminophylline, Amobarbital, Ephedrine interacts with For Daytime — through 6 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedEphedrine, Stimulant Drugs Major
Interaction Summary
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Read the full Green Tea Extract, Decaffeinated + Aminophylline, Amobarbital, Ephedrine interactionSage ExtractCns Depressants, Anticonvulsants Moderate
Interaction Summary
Theoretically, taking sage might increase the sedative and adverse effects of CNS depressants.
Read the full Sage Extract + Aminophylline, Amobarbital, Ephedrine interactionSeleniumBarbiturates Moderate
Interaction Summary
Theoretically, selenium might prolong the sedating effects of barbiturates.
Read the full Selenium + Aminophylline, Amobarbital, Ephedrine interactionShodenCns Depressants Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Shoden + Aminophylline, Amobarbital, Ephedrine interactionAffronCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use of saffron and CNS depressants might have additive sedative effects.
Read the full Affron + Aminophylline, Amobarbital, Ephedrine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Aminophylline, Amobarbital, Ephedrine interactionAtorvastatinAtorvaliq
How Atorvastatin interacts with For Daytime — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedAtorvastatin (lipitor), Organic Anion-transporting Polypeptide Substrates (oatp) +2 Major
Interaction Summary
Green tea extract seems to reduce the levels and clinical effects of atorvastatin.
Read the full Green Tea Extract, Decaffeinated + Atorvastatin interactionShodenCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Shoden + Atorvastatin interactionSage ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, sage might increase the levels and clinical effects of drugs metabolized by CYP3A4.
Read the full Sage Extract + Atorvastatin interactionAtorvastatin CalciumLipitor
How Atorvastatin Calcium interacts with For Daytime — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +2 Major
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract, Decaffeinated + Atorvastatin Calcium interactionShodenCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Shoden + Atorvastatin Calcium interactionSage ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, sage might increase the levels and clinical effects of drugs metabolized by CYP3A4.
Read the full Sage Extract + Atorvastatin Calcium interactionBendroflumethiazide, NadololCorzide
How Bendroflumethiazide, Nadolol interacts with For Daytime — through 6 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedDiuretic Drugs, Nadolol (corgard) Major
Interaction Summary
Theoretically, using green tea with diuretic drugs might increase the risk of hypokalemia.
Read the full Green Tea Extract, Decaffeinated + Bendroflumethiazide, Nadolol interactionL-theanineAntihypertensive Drugs Moderate
Interaction Summary
Theanine might lower blood pressure, potentiating the effects of antihypertensive drugs.
Read the full L-theanine + Bendroflumethiazide, Nadolol interactionSage ExtractAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, sage might increase or decrease the effects of antihypertensive drugs.
Read the full Sage Extract + Bendroflumethiazide, Nadolol interactionShodenAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with antihypertensive drugs might increase the risk of hypotension.
Read the full Shoden + Bendroflumethiazide, Nadolol interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Bendroflumethiazide, Nadolol interactionAffronAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, concomitant use of saffron with antihypertensive drugs might have additive effects.
Read the full Affron + Bendroflumethiazide, Nadolol interactionCarbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine TannateQuadratuss, Ry Tuss, Rynatuss, Tri Tannate Plus
How Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interacts with For Daytime — through 4 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedCytochrome P450 3a4 (cyp3a4) Substrates, Ephedrine +1 Major
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Extract, Decaffeinated + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionSage ExtractAnticholinergic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, sage might decrease the clinical effects of anticholinergic drugs.
Read the full Sage Extract + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionShodenCytochrome P450 3a4 (cyp3a4) Substrates, Serotonergic Drugs Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Shoden + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionL-theanineSerotonergic Drugs Minor
Interaction Summary
Clinical studies regarding the effects of L-theanine on serotonin levels are conflicting.
Read the full L-theanine + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionDyphylline, Ephedrine, Guaifenesin, PhenobarbitalLufyllin-EPG
How Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interacts with For Daytime — through 7 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedStimulant Drugs, Phenobarbital (luminal) +1 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Extract, Decaffeinated + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionShodenCns Depressants Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Shoden + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionVitamin B6Phenobarbital (luminal) Moderate
Interaction Summary
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Read the full Vitamin B6 + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionAffronCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use of saffron and CNS depressants might have additive sedative effects.
Read the full Affron + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionSeleniumBarbiturates Moderate
Interaction Summary
Theoretically, selenium might prolong the sedating effects of barbiturates.
Read the full Selenium + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionSage ExtractCns Depressants Moderate
Interaction Summary
Theoretically, taking sage might increase the sedative and adverse effects of CNS depressants.
Read the full Sage Extract + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionEphedrine, Guaifenesin (otc Drug)Ephedrine Formula 400, Ephedrine Plus Tabs
How Ephedrine, Guaifenesin (otc Drug) interacts with For Daytime — through 1 ingredient. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedStimulant Drugs, Ephedrine Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Extract, Decaffeinated + Ephedrine, Guaifenesin (otc Drug) interactionEphedrine, Guaifenesin, Phenobarbital, TheophyllineMudrane GG
How Ephedrine, Guaifenesin, Phenobarbital, Theophylline interacts with For Daytime — through 7 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedTheophylline, Phenobarbital (luminal) +2 Major
Interaction Summary
Theoretically, green tea might increase the levels and adverse effects of theophylline.
Read the full Green Tea Extract, Decaffeinated + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionSeleniumBarbiturates Moderate
Interaction Summary
Theoretically, selenium might prolong the sedating effects of barbiturates.
Read the full Selenium + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionShodenCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Shoden + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionSage ExtractCns Depressants Moderate
Interaction Summary
Theoretically, taking sage might increase the sedative and adverse effects of CNS depressants.
Read the full Sage Extract + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionAffronCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use of saffron and CNS depressants might have additive sedative effects.
Read the full Affron + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionVitamin B6Phenobarbital (luminal) Moderate
Interaction Summary
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Read the full Vitamin B6 + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionEphedrine, Hydroxyzine, TheophyllineAmi Rax, Marax
How Ephedrine, Hydroxyzine, Theophylline interacts with For Daytime — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedStimulant Drugs, Theophylline +1 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Extract, Decaffeinated + Ephedrine, Hydroxyzine, Theophylline interactionSage ExtractAnticholinergic Drugs Moderate
Interaction Summary
Theoretically, sage might decrease the clinical effects of anticholinergic drugs.
Read the full Sage Extract + Ephedrine, Hydroxyzine, Theophylline interactionShodenCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Shoden + Ephedrine, Hydroxyzine, Theophylline interactionEphedrine, Phenobarbital, Potassium Iodide, TheophyllineMudrane, Quadrinal
How Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interacts with For Daytime — through 7 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedStimulant Drugs, Theophylline +2 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Extract, Decaffeinated + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionSeleniumBarbiturates Moderate
Interaction Summary
Theoretically, selenium might prolong the sedating effects of barbiturates.
Read the full Selenium + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionVitamin B6Phenobarbital (luminal) Moderate
Interaction Summary
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Read the full Vitamin B6 + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionShodenCns Depressants Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Shoden + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionAffronCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use of saffron and CNS depressants might have additive sedative effects.
Read the full Affron + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionSage ExtractCns Depressants Moderate
Interaction Summary
Theoretically, taking sage might increase the sedative and adverse effects of CNS depressants.
Read the full Sage Extract + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionEphedrine, Phenobarbital, TheophyllineTedral
How Ephedrine, Phenobarbital, Theophylline interacts with For Daytime — through 7 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedStimulant Drugs, Theophylline +2 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Extract, Decaffeinated + Ephedrine, Phenobarbital, Theophylline interactionSage ExtractCns Depressants, Anticonvulsants Moderate
Interaction Summary
Theoretically, taking sage might increase the sedative and adverse effects of CNS depressants.
Read the full Sage Extract + Ephedrine, Phenobarbital, Theophylline interactionSeleniumBarbiturates Moderate
Interaction Summary
Theoretically, selenium might prolong the sedating effects of barbiturates.
Read the full Selenium + Ephedrine, Phenobarbital, Theophylline interactionAffronCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use of saffron and CNS depressants might have additive sedative effects.
Read the full Affron + Ephedrine, Phenobarbital, Theophylline interactionVitamin B6Phenobarbital (luminal) Moderate
Interaction Summary
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Read the full Vitamin B6 + Ephedrine, Phenobarbital, Theophylline interactionShodenCns Depressants Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Shoden + Ephedrine, Phenobarbital, Theophylline interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Ephedrine, Phenobarbital, Theophylline interactionEzetimibe, AtorvastatinLiptruzet
How Ezetimibe, Atorvastatin interacts with For Daytime — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedOrganic Anion-transporting Polypeptide Substrates (oatp), Atorvastatin (lipitor) +2 Major
Interaction Summary
Theoretically, green tea might reduce the absorption of organic anion-transporting polypeptide (OATP) substrates.
Read the full Green Tea Extract, Decaffeinated + Ezetimibe, Atorvastatin interactionShodenCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Shoden + Ezetimibe, Atorvastatin interactionSage ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, sage might increase the levels and clinical effects of drugs metabolized by CYP3A4.
Read the full Sage Extract + Ezetimibe, Atorvastatin interactionNadololCorgard, Nadolol
How Nadolol interacts with For Daytime — through 6 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedNadolol (corgard) Major
Interaction Summary
Green tea seems to reduce the levels and clinical effects of nadolol.
Read the full Green Tea Extract, Decaffeinated + Nadolol interactionL-theanineAntihypertensive Drugs Moderate
Interaction Summary
Theanine might lower blood pressure, potentiating the effects of antihypertensive drugs.
Read the full L-theanine + Nadolol interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Nadolol interactionShodenAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with antihypertensive drugs might increase the risk of hypotension.
Read the full Shoden + Nadolol interactionAffronAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, concomitant use of saffron with antihypertensive drugs might have additive effects.
Read the full Affron + Nadolol interactionSage ExtractAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, sage might increase or decrease the effects of antihypertensive drugs.
Read the full Sage Extract + Nadolol interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with For Daytime — through 3 ingredients. Tap an ingredient for the detail:
SeleniumImmunosuppressants Moderate
Interaction Summary
Theoretically, selenium supplementation may reduce the effectiveness of immunosuppressant therapy.
Read the full Selenium + 6-mercaptopurine interactionGreen Tea Extract, DecaffeinatedHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract, Decaffeinated + 6-mercaptopurine interactionShodenHepatotoxic Drugs, Immunosuppressants Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Shoden + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with For Daytime — through 3 ingredients. Tap an ingredient for the detail:
Sage ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, sage might increase the levels and clinical effects of drugs metabolized by CYP3A4.
Read the full Sage Extract + Ado-trastuzumab Emtansine interactionGreen Tea Extract, DecaffeinatedCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Extract, Decaffeinated + Ado-trastuzumab Emtansine interactionShodenCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Shoden + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with For Daytime — through 2 ingredients. Tap an ingredient for the detail:
ShodenHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Shoden + Abacavir Sulfate, Dolutegravir, Lamivudine interactionGreen Tea Extract, DecaffeinatedHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract, Decaffeinated + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with For Daytime — through 2 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract, Decaffeinated + Abacavir, Lamivudine interactionShodenHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Shoden + Abacavir, Lamivudine interactionAbametapirXeglyze
How Abametapir interacts with For Daytime — through 1 ingredient. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedCytochrome P450 1a2 (cyp1a2) Inhibitors Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Read the full Green Tea Extract, Decaffeinated + Abametapir interactionAbciximabReoPro
How Abciximab interacts with For Daytime — through 2 ingredients. Tap an ingredient for the detail:
SeleniumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Selenium + Abciximab interactionGreen Tea Extract, DecaffeinatedAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea Extract, Decaffeinated + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with For Daytime — through 3 ingredients. Tap an ingredient for the detail:
Sage ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, sage might increase the levels and clinical effects of drugs metabolized by CYP3A4.
Read the full Sage Extract + Abemaciclib interactionGreen Tea Extract, DecaffeinatedCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Extract, Decaffeinated + Abemaciclib interactionShodenCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Shoden + Abemaciclib interactionAbiraterone
How Abiraterone interacts with For Daytime — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Extract, Decaffeinated + Abiraterone interactionSage ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, sage might increase the levels and clinical effects of drugs metabolized by CYP3A4.
Read the full Sage Extract + Abiraterone interactionShodenCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Shoden + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with For Daytime — through 3 ingredients. Tap an ingredient for the detail:
ShodenHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Shoden + Abiraterone Acetate interactionGreen Tea Extract, DecaffeinatedHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract, Decaffeinated + Abiraterone Acetate interactionSage ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, sage might increase the levels and clinical effects of drugs metabolized by CYP3A4.
Read the full Sage Extract + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with For Daytime — through 4 ingredients. Tap an ingredient for the detail:
Sage ExtractCytochrome P450 2c19 (cyp2c19) Substrates, Cytochrome P450 2c9 (cyp2c9) Substrates Moderate
Interaction Summary
Theoretically, sage might increase the levels and clinical effects of drugs metabolized by CYP2C19.
Read the full Sage Extract + Abrocitinib interactionGreen Tea Extract, DecaffeinatedAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea Extract, Decaffeinated + Abrocitinib interactionShodenImmunosuppressants Moderate
Interaction Summary
Theoretically, taking ashwagandha might decrease the effects of immunosuppressants.
Read the full Shoden + Abrocitinib interactionSeleniumAnticoagulant/antiplatelet Drugs, Immunosuppressants Moderate
Interaction Summary
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Selenium + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with For Daytime — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Green tea might increase the levels and adverse effects of P-glycoprotein (P-gp) substrates.
Read the full Green Tea Extract, Decaffeinated + Acalabrutinib interactionSage ExtractCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, sage might increase the levels and clinical effects of drugs metabolized by CYP3A4.
Read the full Sage Extract + Acalabrutinib interactionShodenCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Shoden + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with For Daytime — through 4 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedHepatotoxic Drugs, Antidiabetes Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract, Decaffeinated + Acarbose interactionShodenAntidiabetes Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Shoden + Acarbose interactionSage ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking sage with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Sage Extract + Acarbose interactionAffronAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, concomitant use of saffron with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Affron + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with For Daytime — through 6 ingredients. Tap an ingredient for the detail:
Vitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Acebutolol interactionAffronAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, concomitant use of saffron with antihypertensive drugs might have additive effects.
Read the full Affron + Acebutolol interactionShodenAntihypertensive Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with antihypertensive drugs might increase the risk of hypotension.
Read the full Shoden + Acebutolol interactionGreen Tea Extract, DecaffeinatedHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract, Decaffeinated + Acebutolol interactionL-theanineAntihypertensive Drugs Moderate
Interaction Summary
Theanine might lower blood pressure, potentiating the effects of antihypertensive drugs.
Read the full L-theanine + Acebutolol interactionSage ExtractAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, sage might increase or decrease the effects of antihypertensive drugs.
Read the full Sage Extract + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with For Daytime — through 2 ingredients. Tap an ingredient for the detail:
SeleniumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Selenium + Acenocoumarol interactionGreen Tea Extract, DecaffeinatedAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea Extract, Decaffeinated + Acenocoumarol interactionAcepromazineAtravet
How Acepromazine interacts with For Daytime — through 5 ingredients. Tap an ingredient for the detail:
Sage ExtractAnticholinergic Drugs, Cns Depressants Moderate
Interaction Summary
Theoretically, sage might decrease the clinical effects of anticholinergic drugs.
Read the full Sage Extract + Acepromazine interactionAffronCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use of saffron and CNS depressants might have additive sedative effects.
Read the full Affron + Acepromazine interactionShodenCns Depressants Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Shoden + Acepromazine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acepromazine interactionGreen Tea Extract, DecaffeinatedPhenothiazines Minor
Interaction Summary
Theoretically, phenothiazines might increase the levels and adverse effects of caffeine.
Read the full Green Tea Extract, Decaffeinated + Acepromazine interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with For Daytime — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Extract, DecaffeinatedHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract, Decaffeinated + Acetaminophen interactionShodenHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Shoden + Acetaminophen interactionSage ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, sage might decrease the levels and clinical effects of drugs metabolized by CYP2E1.
Read the full Sage Extract + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with For Daytime — through 4 ingredients. Tap an ingredient for the detail:
Sage ExtractCytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, sage might decrease the levels and clinical effects of drugs metabolized by CYP2E1.
Read the full Sage Extract + Acetaminophen, Aspirin interactionGreen Tea Extract, DecaffeinatedAnticoagulant/antiplatelet Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea Extract, Decaffeinated + Acetaminophen, Aspirin interactionSeleniumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Selenium + Acetaminophen, Aspirin interactionShodenCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Shoden + Acetaminophen, Aspirin interactionEach ingredient & the kinds of drugs it affects
For each ingredient in For Daytime with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Shoden
Antidiabetes Drugs
Theoretically, taking ashwagandha with antidiabetes drugs might increase the risk of hypoglycemia.
There is preliminary clinical evidence suggesting that ashwagandha might lower blood glucose levels. Theoretically, ashwagandha might have additive effects when used with antidiabetes drugs and increase the risk of hypoglycemia.
Antihypertensive Drugs
Theoretically, taking ashwagandha with antihypertensive drugs might increase the risk of hypotension.
Animal research suggests that ashwagandha might lower systolic and diastolic blood pressure. Theoretically, ashwagandha might have additive effects when used with antihypertensive drugs and increase the risk of hypotension.
Benzodiazepines
Theoretically, taking ashwagandha might increase the sedative effects of benzodiazepines.
There is preliminary evidence that ashwagandha might have an additive effect with diazepam (Valium) and clonazepam (Klonopin). This may also occur with other benzodiazepines.
Cns Depressants
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Ashwagandha seems to have sedative effects. Theoretically, this may potentiate the effects of barbiturates, other sedatives, and anxiolytics.
Hepatotoxic Drugs
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Ashwagandha has been linked to cases of acute hepatitis, liver failure, hepatic encephalopathy, autoimmune hepatitis, the need for liver transplantation, and death due to liver failure.
Immunosuppressants
Theoretically, taking ashwagandha might decrease the effects of immunosuppressants.
Ashwagandha has demonstrated immunostimulant effects in humans. Animal research has shown that ashwagandha can attenuate the immunosuppression caused by cyclophosphamide.
Thyroid Hormone
Ashwagandha might increase the effects and adverse effects of thyroid hormone.
Concomitant use of ashwagandha with thyroid hormones may cause additive therapeutic and adverse effects. Preliminary clinical research and animal studies suggest that ashwagandha boosts thyroid hormone synthesis and secretion. In one clinical study, ashwagandha increased triiodothyronine (T3) and thyroxine (T4) levels by 41.5% and 19.6%, respectively, and reduced serum TSH levels by 17.4% from baseline in adults with subclinical hypothyroidism.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
In vitro research shows that ashwagandha extract induces CYP1A2 enzymes.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
In vitro research shows that ashwagandha extract induces CYP3A4 enzymes.
Serotonergic Drugs
Some animal studies have reported that ashwagandha can enhance serotonergic transmission by altering certain serotonin (5-HT) receptors. However, there is no evidence to suggest that ashwagandha increases the risk of serotonin-related effects, and there have been no published case reports of serotonin syndrome when combined with other serotonergic drugs. Nevertheless, due to the lack of extensive studies on the matter and the fact that ashwagandha appears to affect serotonergic pathways, it would be prudent to exercise caution when combining it with drugs that affect serotonin. [References: - Effects of Withania somnifera (Ashwaga ndha) on Stress and the Stress-Related Neuropsychiatric Disorders Anxiety, Depression, and Insomnia. Curr Neuropharmacol. 2021 Sep 14; 19: 1468–1495. - A Prospective, Randomized Double-Blind, Placebo-Controlled Study of Safety and Efficacy of a High-Concentration Full-Spectrum Extract of Ashwagandha Root in Reducing Stress and Anxiety in Adults. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3573577/]
Sage Extract
Anticholinergic Drugs
Theoretically, sage might decrease the clinical effects of anticholinergic drugs.
In vitro evidence suggests that common sage (Salvia officinalis) and Spanish sage (Salvia lavandulaefolia) can inhibit acetylcholinesterase and might increase acetylcholine levels.
Anticonvulsants
Theoretically, sage might interfere with the clinical effects of anticonvulsant drugs.
Some species of sage can cause convulsions when consumed in large quantities.
Antidiabetes Drugs
Theoretically, taking sage with antidiabetes drugs might increase the risk of hypoglycemia.
In patients with polycystic ovary syndrome (PCOS) or inadequately controlled type 2 diabetes, common sage (Salvia officinalis) has demonstrated hypoglycemic activity. However, other clinical research in patients with inadequately controlled type 2 diabetes shows that common sage extract does not lower fasting blood glucose levels.
Antihypertensive Drugs
Theoretically, sage might increase or decrease the effects of antihypertensive drugs.
Animal research suggests that common sage (Salvia officinalis) can cause prolonged blood pressure reduction. However, clinical research suggests that Spanish sage (Salvia lavandulaefolia) can increase blood pressure in some people with hypertension. Until more is known, use with caution.
Benzodiazepines
Theoretically, taking sage might increase the sedative and adverse effects of benzodiazepines.
In vitro evidence suggests that certain components of common sage (Salvia officinalis) can bind to benzodiazepine receptors. This effect has not been reported in humans.
Cholinergic Drugs
Theoretically, sage might have additive effects when used with cholinergic drugs.
In vitro evidence suggests that common sage (Salvia officinalis) and Spanish sage (Salvia lavandulaefolia) can inhibit acetylcholinesterase and might increase acetylcholine levels.
Cns Depressants
Theoretically, taking sage might increase the sedative and adverse effects of CNS depressants.
Some constituents of sage have CNS depressant activity.
Cytochrome P450 2C19 (Cyp2C19) Substrates
Theoretically, sage might increase the levels and clinical effects of drugs metabolized by CYP2C19.
In vitro evidence suggests that aqueous extracts of sage can inhibit CYP2C19. So far, this interaction has not been reported in humans.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, sage might increase the levels and clinical effects of drugs metabolized by CYP2C9.
In vitro evidence suggests that aqueous extracts of sage can inhibit CYP2C9. So far, this interaction has not been reported in humans.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, sage might increase the levels and clinical effects of drugs metabolized by CYP2D6.
In vitro evidence suggests that aqueous extracts of sage can inhibit CYP2D6. So far, this interaction has not been reported in humans.
Cytochrome P450 2E1 (Cyp2E1) Substrates
Theoretically, sage might decrease the levels and clinical effects of drugs metabolized by CYP2E1.
Animal research suggests that drinking common sage (Salvia officinalis) tea increases the expression of CYP2E1. So far, this interaction has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, sage might increase the levels and clinical effects of drugs metabolized by CYP3A4.
In vitro evidence suggests that aqueous extracts of sage can inhibit CYP3A4. So far, this interaction has not been reported in humans.
Estrogens
Theoretically, sage might interfere with hormone therapy.
In vitro evidence suggests that geraniol, a constituent of Spanish sage (Salvia lavandulaefolia), exerts estrogenic activity. The clinical significance of this effect is unclear.
P-Glycoprotein Substrates
Theoretically, sage might increase levels of drugs transported by P-glycoprotein.
In vitro research suggests that common sage (Salvia officinalis) can inhibit the multi-drug transporter protein, P-glycoprotein. This effect has not been reported in humans.
Green Tea Extract, Decaffeinated
Atorvastatin (Lipitor)
Green tea extract seems to reduce the levels and clinical effects of atorvastatin.
In healthy humans, taking green tea extract 300 mg or 600 mg along with atorvastatin reduces plasma levels of atorvastatin by approximately 24%. The elimination of atorvastatin is not affected. Atorvastatin is a substrate of organic anion-transporting polypeptides (OATPs). Research shows that two of the major catechins found in green tea, epicatechin gallate (ECG) and epigallocatechin gallate (EGCG), inhibit OATPs. Some OATPs are expressed in the small intestine and are responsible for the uptake of drugs and other compounds, which may have resulted in reduced plasma levels of atorvastatin. It is not clear if drinking green tea alters the absorption of atorvastatin.
Ephedrine
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Green tea contains caffeine. There is evidence that using ephedrine with caffeine might increase the risk of serious life-threatening or debilitating adverse effects such as hypertension, myocardial infarction, stroke, seizures, and death.
Nadolol (Corgard)
Green tea seems to reduce the levels and clinical effects of nadolol.
Preliminary clinical research shows that green tea consumption reduces plasma concentrations of nadolol. Compared to a control group, both peak levels and total drug exposure (AUC) of nadolol were reduced by approximately 85% in subjects who drank green tea daily for two weeks. Drinking green tea with nadolol also significantly reduced nadolol's systolic blood pressure lowering effect. Other clinical research shows that a single dose of green tea can affect plasma nadolol levels for at least one hour. Green tea catechins have been shown to inhibit organic anion transporting polypeptides (OATP), one of which, OATP1A2, is involved in the uptake of nadolol in the intestine The interaction is thought to be due primarily to the epigallocatechin gallate (EGCG) content of green tea.
5-Fluorouracil
Theoretically, high doses of green tea might increase the effects and side effects of 5-fluorouracil.
Animal research shows that taking green tea in amounts equivalent to about 6 cups daily in humans for 4 weeks prior to receiving a single injection of 5-fluorouracil increases the maximum plasma levels of 5-fluorouracil by about 2.5-fold and the area under the curve by 425%.
Adenosine (Adenocard)
Theoretically, green tea might decrease the vasodilatory effects of adenosine and interfere with its use prior to stress testing.
Green tea contains caffeine. Caffeine is a competitive inhibitor of adenosine at the cellular level. However, caffeine doesn't seem to affect supplemental adenosine because high interstitial levels of adenosine overcome the antagonistic effects of caffeine. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. However, methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Anticoagulant/Antiplatelet Drugs
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Conflicting reports exist regarding the effect of green tea on bleeding risk when used with anticoagulant or antiplatelet drugs; however, most evidence suggests that drinking green tea in moderate amounts is unlikely to cause a significant interaction. Green tea contains small amounts of vitamin K, approximately 7 mcg per cup. Some case reports have associated the antagonism of warfarin with the vitamin K content of green tea. However, these reports are rare, and very large doses of green tea (about 8-16 cups daily) appear to be needed to cause these effects. Furthermore, the catechins and caffeine in green tea are reported to have antiplatelet activity.
Beta-Adrenergic Agonists
Green tea contains caffeine. Theoretically, concomitant use of large amounts of caffeine might increase cardiac inotropic effects of beta-agonists.
Bortezomib (Velcade)
Theoretically, green tea might interfere with the effects of bortezomib.
In vitro research shows that green tea polyphenols, such as epigallocatechin gallate (EGCG), interact with bortezomib and block its proteasome inhibitory action. This prevents the induction of cell death in multiple myeloma or glioblastoma cancer cell lines. Advise patients taking bortezomib, not to take green tea.
Carbamazepine (Tegretol)
Theoretically, green tea might reduce the effects of carbamazepine and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that taking caffeine can lower the anticonvulsant effects of carbamazepine and can induce seizures when taken in doses above 400 mg/kg. Human research has shown that taking caffeine 300 mg in three divided doses along with carbamazepine 200 mg reduces the bioavailability of carbamazepine by 32% and prolongs the plasma half-life of carbamazepine 2-fold in healthy individuals.
Celiprolol (Celicard)
Theoretically, green tea might reduce the levels and clinical effects of celiprolol.
In a small human study, taking green tea daily for 4 days appears to decrease blood and urine levels of celiprolol by at least 98%. This interaction is possibly due to the inhibition of organic anion transporting polypeptide (OATP). Green tea catechins have been shown to inhibit organic anion transporting polypeptides (OATP), one of which, OATP1A2, is found in the intestine The interaction is thought to be due primarily to the epigallocatechin gallate (EGCG) content of green tea.
Cimetidine (Tagamet)
Theoretically, concomitant use might increase the effects and adverse effects of caffeine in green tea.
Green tea contains caffeine. Cimetidine can reduce caffeine clearance by 31% to 42%.
Clozapine (Clozaril)
Theoretically, green tea might increase the levels and adverse effects of clozapine and acutely exacerbate psychotic symptoms.
Animal research suggests that, although green tea extract does not affect the elimination of clozapine, it delays the time to reach peak concentration and reduces the peak plasma levels. Also, concomitant administration of green tea and clozapine might theoretically cause acute exacerbation of psychotic symptoms due to the caffeine in green tea. Caffeine can increase the effects and toxicity of clozapine. Caffeine doses of 400-1000 mg daily inhibit clozapine metabolism. Clozapine is metabolized by cytochrome P450 1A2 (CYP1A2). Researchers speculate that caffeine might inhibit CYP1A2. However, there is no reliable evidence that caffeine affects CYP1A2. There is also speculation that genetic factors might make some patients be more sensitive to the interaction between clozapine and caffeine.
Contraceptive Drugs
Theoretically, concomitant use might increase the effects and adverse effects of caffeine found in green tea.
Green tea contains caffeine. Oral contraceptives can decrease caffeine clearance by 40% to 65%.
Cytochrome P450 1A2 (Cyp1A2) Inhibitors
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Caffeine is metabolized by cytochrome P450 1A2 (CYP1A2),. Theoretically, drugs that inhibit CYP1A2 may decrease the clearance rate of caffeine from green tea and increase caffeine levels.
Dipyridamole (Persantine)
Theoretically, green tea might decrease the vasodilatory effects of dipyridamole and interfere with its use prior to stress testing.
Green tea contains caffeine. Caffeine might inhibit dipyridamole-induced vasodilation. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. Methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Disulfiram (Antabuse)
Theoretically, disulfiram might increase the risk of adverse effects from caffeine.
In human research, disulfiram decreases the clearance and increases the half-life of caffeine.
Diuretic Drugs
Theoretically, using green tea with diuretic drugs might increase the risk of hypokalemia.
Green tea contains caffeine. In excessive amounts, caffeine can reduce potassium levels due to stimulation of the sodium-potassium pump. Diuretics can also cause lower potassium levels.
Estrogens
Theoretically, estrogens might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Estrogen inhibits caffeine metabolism.
Ethosuximide (Zarontin)
Theoretically, green tea might reduce the effects of ethosuximide and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that caffeine 92.4 mg/kg can decrease the anticonvulsant activity of ethosuximide. However, this effect has not been reported in humans.
Felbamate (Felbatol)
Theoretically, green tea might reduce the effects of felbamate and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that a high dose of caffeine 161.7 mg/kg can decreases the anticonvulsant activity of felbamate. However, this effect has not been reported in humans.
Fexofenadine (Allegra)
Green tea can decrease blood levels of fexofenadine.
Clinical research shows that green tea can significantly decrease blood levels and excretion of fexofenadine. Taking green tea extract with a dose of fexofenadine decreased bioavailability of fexofenadine by about 30%. In vitro, green tea inhibits the cellular accumulation of fexofenadine by inhibiting the organic anion transporting polypeptide (OATP) drug transporter. Research shows that two of the major catechins found in green tea, epicatechin gallate (ECG) and epigallocatechin gallate (EGCG), inhibit OATPs, specifically OATP1A2, OATP1B1, and OATP2B1. In addition, green tea has been shown to reduce the absorption of some drugs that are OATP substrates.
Flutamide (Eulexin)
Theoretically, green tea might increase the levels and adverse effects of flutamide.
Green tea contains caffeine. In vitro evidence suggests that caffeine can inhibit the metabolism of flutamide. Theoretically, concomitant use of caffeine and flutamide might increase serum concentrations of flutamide and increase the risk adverse effects.
Fluvoxamine (Luvox)
Theoretically, fluvoxamine might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Fluvoxamine reduces caffeine metabolism.
Hepatotoxic Drugs
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Green tea extract supplements have been linked to several cases of hepatotoxicity and might have additive hepatotoxic effects with other drugs..
Imatinib (Gleevec)
Theoretically, green tea might reduce the levels and clinical effects of imatinib.
In animal research, a single dose of green tea extract reduces the area under the curve (AUC) of imatinib by up to approximately 64% and its main metabolite N-desmethyl imatinib by up to approximately 81%. This interaction has not been shown in humans. The mechanism of action is unclear but may involve multiple pathways.
L-Theanine
Antihypertensive Drugs
Theanine might lower blood pressure, potentiating the effects of antihypertensive drugs.
Animal research shows that theanine can lower blood pressure in spontaneously hypertensive animals. Theoretically, concomitant use of theanine and antihypertensive drugs might potentiate the antihypertensive activity.
Cns Depressants
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants. However, it is unclear if this concern is clinically relevant.
Theoretically, theanine may compete with glutamate and/or increase plasma gamma-aminobutyric acid (GABA) levels, which could cause CNS depression. In one clinical study, some subjects taking oral theanine reported drowsiness.
Serotonergic Drugs
Clinical studies regarding the effects of L-theanine on serotonin levels are conflicting. Some studies suggest it can increase serotonin levels in the brain while others report that it may decrease them. Nevertheless, there have been no reports of l-theanine being a causative agent in serotonergic-related side effects or serotonin syndrome.
Affron
Antidiabetes Drugs
Theoretically, concomitant use of saffron with antidiabetes drugs might increase the risk of hypoglycemia.
Some clinical research shows that taking saffron extract reduces fasting levels of glucose when used in addition to hypoglycemic agents. However, saffron powder itself has not been shown to reduce fasting glucose levels.
Antihypertensive Drugs
Theoretically, concomitant use of saffron with antihypertensive drugs might have additive effects.
Animal and human research suggests that saffron extract can decrease blood pressure.
Caffeine
Theoretically, saffron might inhibit the metabolism of caffeine.
A small clinical study suggests that taking saffron powder 300 mg in 150 mL water daily for 5 days and then taking caffeine 200 mg seems to reduce caffeine metabolite levels in the saliva and urine in males, but not females. Theoretically, this may be due to the inhibition of cytochrome P450 1A2 by saffron.
Cns Depressants
Theoretically, concomitant use of saffron and CNS depressants might have additive sedative effects.
Clinical research shows that taking saffron extract 60 mg orally daily for 26 weeks can cause drowsiness and sedation. Animal research suggests that adding saffron to hexobarbital further increases sleeping and slows motor activity.
Selenium
Anticoagulant/Antiplatelet Drugs
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Clinical research suggests that taking selenium 10 mcg/kg/day can increase bleeding times by increasing prostacyclin production, which inhibits platelet activity. Other clinical research suggests that taking selenium 75 mcg daily, in combination with ascorbic acid 600 mg, alpha-tocopherol 300 mg, and beta-carotene 27 mg, reduces platelet aggregation.
Barbiturates
Theoretically, selenium might prolong the sedating effects of barbiturates.
Laboratory research suggests that selenium can inhibit the hepatic metabolism of barbiturates. Selenium seems to prolong the sedative effect of pentobarbital in animal models.
Immunosuppressants
Theoretically, selenium supplementation may reduce the effectiveness of immunosuppressant therapy.
In vitro research and preliminary clinical evidence suggests that selenium may stimulate the immune system.
Warfarin (Coumadin)
Theoretically, selenium might interfere with warfarin activity.
Animal research suggests that selenium can increase warfarin activity. Selenium might interact with warfarin by displacing it from albumin binding sites, reducing its metabolism in the liver, or by decreasing production of vitamin K-dependent clotting factors. Selenium can also prolong bleeding times in humans by increasing prostacyclin production, which inhibits platelet activity.
Contraceptive Drugs
Contraceptive drugs might increase levels of selenium, although the clinical significance of this effect is unclear.
Some research suggests that oral contraceptives increase serum selenium levels in women taking oral contraceptives; however, other research shows no change in selenium levels. It is suggested that an increase could be due to increased carrier proteins, indicating a redistribution of selenium rather than a change in total body selenium.
Niacin
Selenium might reduce the beneficial effects of niacin on high-density lipoprotein (HDL) levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as selenium, or to the combination. It also is not known whether it will occur in other patient populations.
Vitamin B6
Amiodarone (Cordarone)
Theoretically, vitamin B6 might increase the photosensitivity caused by amiodarone.
Despite initial case reports suggesting that pyridoxine may have a protective effect against amiodarone-induced photosensitivity, preliminary clinical research suggests that pyridoxine may actually exacerbate this adverse effect.
Antihypertensive Drugs
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Research in hypertensive rats shows that vitamin B6 can decrease systolic blood pressure. Similarly, clinical research in patients with hypertension shows that taking high doses of vitamin B6 may reduce systolic and diastolic blood pressure, possibly by reducing plasma levels of epinephrine and norepinephrine.
Phenobarbital (Luminal)
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenobarbital, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenobarbital to avoid high doses of vitamin B6.
Phenytoin (Dilantin)
High doses of vitamin B6 may reduce the levels and clinical effects of phenytoin.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenytoin, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenytoin to avoid high doses of vitamin B6.
Levodopa
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Vitamin B6 (pyridoxine) enhances the metabolism of levodopa, reducing its clinical effects. However, this interaction does not occur when carbidopa is used concurrently with levodopa (Sinemet). Therefore, it is not likely to be a problem in most people.
Vitamin B12
Metformin (Glucophage)
Metformin, a common medication used to manage type 2 diabetes, has been associated with lower vitamin B12 levels in some individuals. Prolonged use of metformin can interfere with the absorption of B12 in the digestive system, potentially leading to a deficiency in this essential vitamin.
Brand information
Manufacturer and brand details for For Daytime, from the product label.
For Daytime by Stasis: Common Questions
Does For Daytime by Stasis interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take this if I'm pregnant?
Can I take this while breastfeeding?
Will this help with anxiety?
What's Affron and why is it in here?
Does this have caffeine?
What if I'm taking metformin for diabetes?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if For Daytime is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind For Daytime’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin B6
Interacts with 210 drugsVitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is best known for helping with pregnancy-rel...
Read the full Vitamin B6 monograph → Herb & supplement monographVitamin B12
Interacts with 20 drugsVitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very helpful for people who are deficient — su...
Read the full Vitamin B12 monograph → Herb & supplement monographTheanine
Interacts with 565 drugsTheanine (usually L-theanine) is an amino acid found naturally in tea leaves that many people take to feel calmer and less stressed without strong drowsiness. Early research suggests it may...
Read the full Theanine monograph → Herb & supplement monographSelenium
Interacts with 321 drugsSelenium is an essential trace mineral your body needs in small amounts for thyroid function, antioxidant defense, and immune health. Most people who eat a varied diet get enough, and supple...
Read the full Selenium monograph → Herb & supplement monographSaffron
Interacts with 521 drugsSaffron is a costly spice that has shown promise in early studies for mild-to-moderate depression and some mood and PMS symptoms, but most research uses small trials, so results are not defi...
Read the full Saffron monograph → Herb & supplement monographGreen Tea
Interacts with 1,293 drugsGreen tea is a popular beverage rich in antioxidants called catechins, and drinking it in normal amounts is considered safe for most people. Concentrated green tea extracts are a different s...
Read the full Green Tea monograph → Herb & supplement monographAshwagandha
Interacts with 1,372 drugsAshwagandha is an Ayurvedic herb most often taken to help with stress, anxiety, and sleep, and some small studies suggest it may help, though the evidence is still limited. It is generally w...
Read the full Ashwagandha monograph → Herb & supplement monographSage
Interacts with 1,296 drugsSage is a common kitchen herb that is generally safe in food amounts and is traditionally used for sore throats, digestion, sweating, and memory. Some early research is encouraging for sore...
Read the full Sage monograph →Sources & How We Checked
For Daytime's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 404 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Vitamin B6 32 references
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Geerling BJ, Dagnelie PC, Badart-Smook A, et al. Diet as a risk factor for the development of ulcerative colitis. Am J Gastroenterol 2000;95:1008-13. PubMed
- South M. Neonatal seizures after pyridoxine use -- reply. Lancet 1999;354:2083. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Baxter P, Aicardi J. Neonatal seizures after pyridoxine use. Lancet 1999;354:2082-3. PubMed
- Bendich A, Cohen M. Vitamin B6 safety issues. Ann N Y Acad Sci 1990;585:321-30.
- Schaumburg H, Kaplan J, Windebank A. Sensory neuropathy from pyridoxine abuse. A new megavitamin syndrome. N Engl J Med 1983;309:445-8. PubMed
- Gordon N. Pyridoxine dependency: an update. Dev Med Child Neurol 1997;39:63-5. PubMed
- Lewis PJ. Pain in the hand and wrist. Pyridoxine supplements may help patients with carpal tunnel syndrome. BMJ 1995;310:1534. PubMed
- Kaufman G. Pyridoxine against amiodarone-induced photosensitivity (letter). Lancet 1984;1:51-2. PubMed
- Mulrow JP, Mulrow CD, McKenna WJ. Pyridoxine and amiodarone-induced photosensitivity. Ann Intern Med 1985;103:68-9. PubMed
- Kawada A, Kashima A, Shiraishi H, et al. Pyridoxine-induced photosensitivity and hypophosphatasia. Dermatology 2000;201:356-60.. PubMed
- Vasile A, Goldberg R, Kornberg B. Pyridoxine toxicity: report of a case. J Am Osteopath Assoc 1984;83:790-1. DOI
- Hansson O, Sillanpaa M. Pyridoxine and serum concentration of phenytoin and phenobarbitone. Lancet 1976;1:256. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Chittumma P, Kaewkiattikun K, Wiriyasiriwach B. Comparison of the effectiveness of ginger and vitamin B6 for treatment of nausea and vomiting in early pregnancy: a randomized double-blind controlled trial. J Med Assoc Thai 2007;90:15-20.
- Hatzitolios, A., Iliadis, F., Katsiki, N., and Baltatzi, M. Is the anti-hypertensive effect of dietary supplements via aldehydes reduction evidence based? A systematic review. Clin Exp.Hypertens. 2008;30(7):628-639. PubMed
- Vasdev, S., Ford, C. A., Parai, S., Longerich, L., and Gadag, V. Dietary vitamin B6 supplementation attenuates hypertension in spontaneously hypertensive rats. Mol.Cell Biochem. 1999;200(1-2):155-162.
- de, Vogel S., Dindore, V., van, Engeland M., Goldbohm, R. A., van den Brandt, P. A., and Weijenberg, M. P. Dietary folate, methionine, riboflavin, and vitamin B-6 and risk of sporadic colorectal cancer. J Nutr 2008;138(12):2372-2378. PubMed
- Hagen, I., Nesheim, B. I., and Tuntland, T. No effect of vitamin B-6 against premenstrual tension. A controlled clinical study. Acta Obstet.Gynecol.Scand. 1985;64(8):667-670. PubMed
- Aybak, M., Sermet, A., Ayyildiz, M. O., and Karakilcik, A. Z. Effect of oral pyridoxine hydrochloride supplementation on arterial blood pressure in patients with essential hypertension. Arzneimittelforschung. 1995;45(12):1271-1273.
- Lal, K. J., Dakshinamurti, K., and Thliveris, J. The effect of vitamin B6 on the systolic blood pressure of rats in various animal models of hypertension. J Hypertens. 1996;14(3):355-363. PubMed
- Lauritzen CH, Reuter HD, Repges R, Bohnert K, and Schmidt U. Treatment of premenstrual tension syndrome with Vitex agnus castus. Controlled, double-blind study versus pyridoxine. Phytomed 1997;4(3):183-189. PubMed
- Fonseca VA, Lavery LA, Thethi TK, et al. Metanx in type 2 diabetes with peripheral neuropathy: A randomized trial. Am J Med 2013;126(2):141-9. PubMed
- Hankey GJ, Eikelboom JW, Yi Q, et al. Treatment with B vitamins and incidence of cancer in patients with previous stroke or transient ischemic attack: Results of a randomized placebo-controlled trial. Stroke 2012;43(6):1572-7. PubMed
- Hoyer-Kuhn H, Kohbrok S, Volland R, Franklin J, Hero B, Beck BB, Hoppe B. Vitamin B6 in primary hyperoxaluria I: first prospective trial after 40 years of practice. Clin J Am Soc Nephrol. 2014 Mar;9(3):468-77. PubMed
- Mahmoud A, Tabassum S, Al Enazi S, et al. Amelioration of levetiracetam-induced behavioral side effects by pyridoxine. A randomized double blind controlled study. Pediatr Neurol 2021;119:15-21. PubMed
- Gupta M, Gallante B, Bamberger JN, et al. Prospective randomized evaluation of idiopathic hyperoxaluria treatments. J Endourol 2021;35(12):1844-1851. PubMed
- Li H, Chen M, Liang S, et al. Excessive vitamin B6 during treatment is related to poor prognosis of patients with nasopharyngeal carcinoma: A U-shaped distribution suggests low dose supplement. Clin Nutr 2021;40(4):2293-2300. PubMed
- Tanigawa J, Nabatame S, Tominaga K, et al. High-dose pyridoxine treatment for inherited glycosylphosphatidylinositol deficiency. Brain Dev 2021;43(6):680-687. PubMed
- Committee on Practice Bulletins-Obstetrics. ACOG Practice Bulletin No. 189: Nausea And Vomiting Of Pregnancy. Obstet Gynecol. 2018;131(1):e15-e30. PubMed
Vitamin B12 30 references
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Hartman TJ, Woodson K, Stolzenberg-Solomon R, et al. Association of the B-vitamins pyridoxal 5'-phosphate (B6), B12, and folate with lung cancer risk in older men. Am J Epidemiol 2001;153:688-94.. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Lange H, Suryapranata H, De Luca G, et al. Folate therapy and in-stent restenosis after coronary stenting. N Engl J Med 2004;350:2673-81. PubMed
- Collin, S. M., Metcalfe, C., Refsum, H., Lewis, S. J., Zuccolo, L., Smith, G. D., Chen, L., Harris, R., Davis, M., Marsden, G., Johnston, C., Lane, J. A., Ebbing, M., Bonaa, K. H., Nygard, O., Ueland, P. M., Grau, M. V., Baron, J. A., Donovan, J. L., Nea
- Geissbuhler, P., Mermillod, B., and Rapin, C. H. Elevated serum vitamin B12 levels associated with CRP as a predictive factor of mortality in palliative care cancer patients: a prospective study over five years. J.Pain Symptom.Manage. 2000;20(2):93-103. PubMed
- Salles, N., Herrmann, F., Sakbani, K., Rapin, C. H., and Sieber, C. High vitamin B12 level: a strong predictor of mortality in elderly inpatients. J Am Geriatr.Soc 2005;53(5):917-918.
- Looker, H. C., Fagot-Campagna, A., Gunter, E. W., Pfeiffer, C. M., Sievers, M. L., Bennett, P. H., Nelson, R. G., Hanson, R. L., and Knowler, W. C. Homocysteine and vitamin B(12) concentrations and mortality rates in type 2 diabetes. Diabetes Metab Res R
- Uhl, W., Nolting, A., Golor, G., Rost, K. L., and Kovar, A. Safety of hydroxocobalamin in healthy volunteers in a randomized, placebo-controlled study. Clin Toxicol (Phila) 2006;44 Suppl 1:17-28. PubMed
- Borron, S. W., Baud, F. J., Barriot, P., Imbert, M., and Bismuth, C. Prospective study of hydroxocobalamin for acute cyanide poisoning in smoke inhalation. Ann Emerg.Med 2007;49(6):794-801, 801. PubMed
- Borron, S. W., Baud, F. J., Megarbane, B., and Bismuth, C. Hydroxocobalamin for severe acute cyanide poisoning by ingestion or inhalation. Am J Emerg.Med 2007;25(5):551-558. PubMed
- Lewis, J. G. Gout, Steatorrhoea, and Megaloblastic Anaemia. Ann Rheum.Dis 1962;21(3):284-286. PubMed
- Tal, S., Shavit, Y., Stern, F., and Malnick, S. Association between vitamin B12 levels and mortality in hospitalized older adults. J Am Geriatr.Soc 2010;58(3):523-526. PubMed
- Baztan, J. J., Gavidia, J. J., Gomez-Pavon, J., Esteve, A., and Ruiperez, I. High vitamin B12 levels and in-hospital mortality. J Am Geriatr.Soc 2010;58(11):2237-2238. PubMed
- Omboni, E., Checchini, M., and Longoni, F. [Hypopotassemia and megaloblastic anemia. Presentation of a case]. Minerva Med 8-31-1987;78(16):1255-1257.
- Aalfs As, Scholvinck LH, Horvath B. Acneiform eruption in a 5-year old due to vitamin B12 supplementation. Eur J Dermatol 2013;23(5):726-7. PubMed
- Balta I, Ozuguz P. Vitamin B12-induced acneiform eruption. Cutan Ocul Toxicol 2014;33(2):94-5. PubMed
- Carman KB, Belgemen T, Yis U. Involuntary movements misdiagnosed as seizure during vitamin B12 treatment. Pediatr Emerg Care 2013;29(11):1223-4. PubMed
- Djuric V, Bogic M, Popadic AP, et al. Anaphylactic reaction to hydroxycobalamin with tolerance to cyanocobalamin. Ann Allergy Asthma Immunol 2012;108(3):207-8. PubMed
- Kartel O, Gulec M, Demirel F, et al. Vitamin B12 allergy and successful desensitization with cyanocobalamin: A case report. Allergol Immunopath (Madr) 2012;40(5):324-5.
- Patiroglu T, Unal E, Yildirim S. Infantile tremor syndrome associated with cobalamin therapy: A case report. Clin Neurol Neurosurg 2013;115(9):1903-5. PubMed
- Schulte S, Barkema LW, Kardaun SH. Long-lasting atypical acneiform eruption with prominent comedones induced by hydroxocobalamin (vitamin B12). J Dtsch Dermatol Ges 2014;12(6):502-3.
- Zanus C, Alberini E, Costa P, et al. Involuntary movements after correction of vitamin B12 deficiency: A video-case report. Epileptic Disord 2012;14(2):174-80. PubMed
- Fanidi A, Carreras-Torres R, Larose TL, et al. Is high vitamin B12 status a cause of lung cancer? Int J Cancer. 2019 Sep 15;145(6):1499-1503. PubMed
- Fujita Y, Mizukami T, Maya Y, et al. Vitamin B12 allergy manifesting as lymphomatoid contact dermatitis. Eur J Dermatol. 2020;30(3):304-305. PubMed
- Dépret F, Hoffmann C, Daoud L, et al. Association between hydroxocobalamin administration and acute kidney injury after smoke inhalation: a multicenter retrospective study. Crit Care. 2019;23(1):421. PubMed
- Khairan P, Sobue T, Eshak ES, et al. Association of dietary intakes of vitamin B12, vitamin B6, folate, and methionine with the risk of esophageal cancer: the Japan Public Health Center-based (JPHC) prospective study. BMC Cancer 2021;21(1):982. PubMed
- Evans J, Pandya A, Ding Y, Qunibi WY. Hydroxocobalamin-Induced Oxalate Nephropathy in a Patient With Smoke Inhalation. Kidney Int Rep 2021;6(8):2228-2231. PubMed
- Lacombe V, Chabrun F, Lacout C, et al. Persistent elevation of plasma vitamin B12 is strongly associated with solid cancer. Sci Rep 2021;11(1):13361. PubMed
- Pegalajar-García MD, Cebolla-Verdugo M, Prados-Carmona Á, Llamas-Segura C, Navarro-Triviño FJ. Systemic allergic dermatitis to cobalt present in cyanocobalamin supplementation. Contact Dermatitis 2023;89(3):203-205. PubMed
Theanine 6 references
- Yokogoshi H, Kobayashi M. Hypotensive effect of gamma-glutamylethylamide in spontaneously hypertensive rats. Life Sci 1998;62:1065-8.
- Haskell, C. F., Kennedy, D. O., Milne, A. L., Wesnes, K. A., and Scholey, A. B. The effects of L-theanine, caffeine and their combination on cognition and mood. Biol.Psychol. 2008;77(2):113-122. PubMed
- Yokogoshi, H., Kato, Y., Sagesaka, Y. M., Takihara-Matsuura, T., Kakuda, T., and Takeuchi, N. Reduction effect of theanine on blood pressure and brain 5-hydroxyindoles in spontaneously hypertensive rats. Biosci.Biotechnol.Biochem. 1995;59(4):615-618. PubMed
- Lyon MR, Kapoor MP, Juneja LR. The effects of L-theanine (Suntheanine®) on objective sleep quality in boys with attention deficit hyperactivity disorder (ADHD): a randomized, double-blind, placebo-controlled clinical trial. Altern Med Rev. 2011;16(4):348-
- Hidese S, Ota M, Wakabayashi C, et al. Effects of chronic l-theanine administration in patients with major depressive disorder: an open-label study. Acta Neuropsychiatr 2017;29(2):72-9.
- Tsuchiya T, Honda H, Oikawa M, et al. Oral administration of the amino acids cystine and theanine attenuates the adverse events of S-1 adjuvant chemotherapy in gastrointestinal cancer patients. Int J Clin Oncol 2016;21(6):1085-90. PubMed
Selenium 36 references
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Trafikowska U, Zachara BA, Wiacek M, et al. Selenium supply and glutathione peroxidase activity in breastfed Polish infants. Acta Paediatr 1996;85:1143-5. PubMed
- Duffield-Lillico AJ, Slate EH, Reid ME, et al. Selenium supplementation and secondary prevention of nonmelanoma skin cancer in a randomized trial. J Natl Cancer Inst 2003;95:1477-81.. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Schiavon R, Freeman GE, Guidi GC, et al. Selenium enhances prostacyclin production by cultured endothelial cells: possible explanation for increased bleeding times in volunteers taking selenium as a dietary supplement. Thromb Res 1984;34:389-96. PubMed
- Davila JC, Edds GT, Osuna O, Simpson CF. Modification of the effects of aflatoxin B1 and warfarin in young pigs given selenium. Am J Vet Res 1983;44:1877-83. DOI
- Heese HD, Lawrence MA, Dempster WS, Pocock F. Reference concentrations of serum selenium and manganese in healthy nulliparas. S Afr Med J 1988;73:163-5.
- Lloyd B, Lloyd RS, Clayton BE. Effect of smoking, alcohol and other factors on the selenium status of a healthy population. J Epidemiol Commun Health 1983;37:213-7. PubMed
- Capel ID, Jenner M, Williams DC, et al. The effect of prolonged oral contraceptive steroid use on erythrocyte glutathione peroxidase activity. J Steroid Biochem 1981;14:729-32. PubMed
- Contempre B, Dumont JE, Ngo B, et al. Effect of selenium supplementation in hypothyroid subjects of an iodine and selenium deficient area: the possible danger of indiscriminate supplementation of iodine-deficient subjects with selenium. J Clin Endocrinol PubMed
- Hofbauer LC, Spitzweg C, Magerstadt RA, Heufelder AE. Selenium-induced thyroid dysfunction. Postgrad Med J 1997;73:103-4. PubMed
- Debski B, Milner JA. Dietary selenium supplementation prolongs pentobarbital induced hypnosis. J Nutr Biochem 2004;15:548-53. PubMed
- Ishikawa M, Sasaki M, Koiwai K, et al. Inhibition of hepatic mixed-function oxidase enzymes in mice by acute and chronic treatment with selenium. J Pharmacobiodyn 1992;15:377-85. PubMed
- Lippmann SM, Klein EA, Goodman PJ, et al. Effect of selenium and vitamin E on risk of prostate cancer and other cancers: the selenium and vitamin E cancer prevention trial (SELECT). JAMA 2009;301:39-51. DOI
- Reid SM, Middleton P, Cossich MC, Crowther CA. Interventions for clinical and subclinical hypothyroidism in pregnancy. Cochrane Database Syst Rev 2010;(7):CD007752. PubMed
- Vinceti, M., Wei, E. T., Malagoli, C., Bergomi, M., and Vivoli, G. Adverse health effects of selenium in humans. Rev.Environ.Health 2001;16(4):233-251. PubMed
- Abrams, C. K., Siram, S. M., Galsim, C., Johnson-Hamilton, H., Munford, F. L., and Mezghebe, H. Selenium deficiency in long-term total parenteral nutrition. Nutr Clin Pract 1992;7(4):175-178. PubMed
- Spiller, H. A. and Pfiefer, E. Two fatal cases of selenium toxicity. Forensic Sci Int 8-24-2007;171(1):67-72. PubMed
- Negro, R., Greco, G., Mangieri, T., Pezzarossa, A., Dazzi, D., and Hassan, H. The influence of selenium supplementation on postpartum thyroid status in pregnant women with thyroid peroxidase autoantibodies. J Clin Endocrinol.Metab 2007;92(4):1263-1268. PubMed
- Alexander, J. Selenium. Novartis.Found.Symp 2007;282:143-149.
- Salonen, J. T., Salonen, R., Seppanen, K., Rinta-Kiikka, S., Kuukka, M., Korpela, H., Alfthan, G., Kantola, M., and Schalch, W. Effects of antioxidant supplementation on platelet function: a randomized pair-matched, placebo-controlled, double-blind trial
- Kupka, R., Mugusi, F., Aboud, S., Msamanga, G. I., Finkelstein, J. L., Spiegelman, D., and Fawzi, W. W. Randomized, double-blind, placebo-controlled trial of selenium supplements among HIV-infected pregnant women in Tanzania: effects on maternal and chil
- Kamble, P., Mohsin, N., Jha, A., Date, A., Upadhaya, A., Mohammad, E., Khalil, M., Pakkyara, A., and Budruddin, M. Selenium intoxication with selenite broth resulting in acute renal failure and severe gastritis. Saudi.J Kidney Dis.Transpl. 2009;20(1):106
- Peretz, A., Neve, J., Desmedt, J., Duchateau, J., Dramaix, M., and Famaey, J. P. Lymphocyte response is enhanced by supplementation of elderly subjects with selenium-enriched yeast. Am.J Clin.Nutr. 1991;53(5):1323-1328. PubMed
- Kumpulainen, J., Salmenpera, L., Siimes, M. A., Koivistoinen, P., and Perheentupa, J. Selenium status of exclusively breast-fed infants as influenced by maternal organic or inorganic selenium supplementation. Am.J Clin.Nutr. 1985;42(5):829-835. PubMed
- Han, L. and Zhou, S. M. Selenium supplement in the prevention of pregnancy induced hypertension. Chin Med J (Engl) 1994;107(11):870-871.
- Kiremidjian-Schumacher, L., Roy, M., Wishe, H. I., Cohen, M. W., and Stotzky, G. Supplementation with selenium and human immune cell functions. II. Effect on cytotoxic lymphocytes and natural killer cells. Biol.Trace Elem.Res. 1994;41(1-2):115-127. PubMed
- Srivastava, A. K., Gupta, B. N., Bihari, V., and Gaur, J. S. Generalized hair loss and selenium exposure. Vet.Hum.Toxicol. 1995;37(5):468-469.
- Sudfeld CR, Aboud S, Kupka R, et al. Effect of selenium supplementation on HIV-1 RNA detection in breast milk of Tanzanian women. Nutrition 2014;30(9):1081-4. PubMed
- Rees K, Hartley L, Day C, et al. Selenium supplementation for the primary prevention of cardiovascular disease. Cochrane Database Syst Rev 2013;1:CD009671. PubMed
- Thompson PA, Ashbeck EL, Roe DJ, et al. Selenium Supplementation for Prevention of Colorectal Adenomas and Risk of Associated Type 2 Diabetes. J Natl Cancer Inst. 2016;108(12). PubMed
- Wichman J, Winther KH, Bonnema SJ, Hegedüs L. Selenium supplementation significantly reduces thyroid autoantibody levels in patients with chronic autoimmune thyroiditis: a systematic review and meta-analysis. Thyroid 2016;26(12):1681-92. PubMed
- Vinceti M, Filippini T, Rothman KJ. Selenium exposure and the risk of type 2 diabetes: a systematic review and meta-analysis. Eur J Epidemiol. 2018 Sep;33(9):789-810. Epub 2018 Jul 5. Review. PubMed
- Fallah S, Sani FV, Firoozrai M. Effect of contraceptive pill on the selenium and zinc status of healthy subjects. Contraception. 2009;80(1):40-3. PubMed
- Malpas CB, Vivash L, Genc S, et al. A Phase IIa Randomized Control Trial of VEL015 (Sodium Selenate) in Mild-Moderate Alzheimer's Disease. J Alzheimers Dis. 2016;54(1):223-232. PubMed
Saffron 22 references
- Blumenthal M, ed. The Complete German Commission E Monographs: Therapeutic Guide to Herbal Medicines. Trans. S. Klein. Boston, MA: American Botanical Council, 1998.
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Feo F, Martinez J, Martinez A, et al. Occupational allergy in saffron workers. Allergy 1997;52:633-41. PubMed
- Wuthrich B, Schmid-Grendelmeyer P, Lundberg M. Anaphylaxis to saffron. Allergy 1997;52:476-7. PubMed
- Akhondzadeh S, Tahmacebi-Pour N, Noorbala AA, et al. Crocus sativus L. in the treatment of mild to moderate depression: a double-blind, randomized and placebo-controlled trial. Phytother Res 2005;19:148-51.
- Safarinejad MR, Shafiei N, Safarinejad S. A prospective double-blind randomized placebo-controlled study of the effect of saffron (Crocus sativus Linn.) on semen parameters and seminal plasma antioxidant capacity in infertile men with idiopathic oligoasth
- Fatehi, M., Rashidabady, T., and Fatehi-Hassanabad, Z. Effects of Crocus sativus petals' extract on rat blood pressure and on responses induced by electrical field stimulation in the rat isolated vas deferens and guinea-pig ileum. J Ethnopharmacol. 2003; PubMed
- Modaghegh, M. H., Shahabian, M., Esmaeili, H. A., Rajbai, O., and Hosseinzadeh, H. Safety evaluation of saffron (Crocus sativus) tablets in healthy volunteers. Phytomedicine. 2008;15(12):1032-1037. PubMed
- Imenshahidi, M., Hosseinzadeh, H., and Javadpour, Y. Hypotensive effect of aqueous saffron extract (Crocus sativus L.) and its constituents, safranal and crocin, in normotensive and hypertensive rats. Phytother.Res 12-9-2009;
- Zhang, Y., Shoyama, Y., Sugiura, M., and Saito, H. Effects of Crocus sativus L. on the ethanol-induced impairment of passive avoidance performances in mice. Biol.Pharm Bull. 1994;17(2):217-221. PubMed
- Wuthrich, B., Schmid-Grendelmeyer, P., and Lundberg, M. Anaphylaxis to saffron. Allergy 1997;52(4):476-477. PubMed
- Akhondzadeh S, Sabet MS, Harirchian MH, Togha M, Cheraghmakani H, Razeghi S, Hejazi SSh, Yousefi MH, Alimardani R, Jamshidi A, Zare F, Moradi A. Saffron in the treatment of patients with mild to moderate Alzheimer's disease: a 16-week, randomized and plac
- Kashani L, Eslatmanesh S, Saedi N, Niroomand N, Ebrahimi M, Hosseinian M, Foroughifar T, Salimi S, Akhondzadeh S. Comparison of Saffron versus Fluoxetine in Treatment of Mild to Moderate Postpartum Depression: A Double-Blind, Randomized Clinical Trial. Ph PubMed
- Kianbakht S, Ghazavi A. Immunomodulatory effects of saffron: a randomized double-blind placebo-controlled clinical trial. Phytother Res. 2011 Dec;25(12):1801-5. PubMed
- Mazidi M, Shemshian M, Mousavi SH, Norouzy A, Kermani T, Moghiman T, Sadeghi A, Mokhber N, Ghayour-Mobarhan M, Ferns GA. A double-blind, randomized and placebo-controlled trial of Saffron (Crocus sativus L.) in the treatment of anxiety and depression. J C
- Safarinejad MR, Shafiei N, Safarinejad S. An open label, randomized, fixed-dose, crossover study comparing efficacy and safety of sildenafil citrate and saffron (Crocus sativus Linn.) for treating erectile dysfunction in men naïve to treatment. Int J Impo PubMed
- Talaei A, Hassanpour Moghadam M, Sajadi Tabassi SA, Mohajeri SA. Crocin, the main active saffron constituent, as an adjunctive treatment in major depressive disorder: a randomized, double-blind, placebo-controlled, pilot clinical trial. J Affect Disord. 2 PubMed
- Azimi P, Ghiasvand R Feizi A, Hariri M, Abbasi B. Effects of cinnamon, cardamom, saffron, and ginger consumption on markers of glycemic control, lipid profile, oxidative stress, and inflammation in type 2 diabetes. Rev Diabet Stud. 2014 Fall-Winter;11(3-4
- Begas E, Bounitsi M, Kilindris T, et al. Effects of short-term saffron (Crocus sativus L.) intake on the in vivo activities of xenobiotic metabolizing enzymes in healthy volunteers. Food Chem Toxicol. 2019;130:32-43. PubMed
- Moravej Aleali A, Amani R, Shahbazian H, Namjooyan F, Latifi SM, Cheraghian B. The effect of hydroalcoholic Saffron (Crocus sativus L.) extract on fasting plasma glucose, HbA1c, lipid profile, liver, and renal function tests in patients with type 2 diabet
- Abbaszadeh-Mashkani S, Hoque SS, Banafshe HR, Ghaderi A. The effect of crocin (the main active saffron constituent) on the cognitive functions, craving, and withdrawal syndrome in opioid patients under methadone maintenance treatment. Phytother Res. 2021; PubMed
Green Tea 219 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Harder S, Fuhr U, Staib AH, Wolff T. Ciprofloxacin-caffeine: a drug interaction established using in vivo and in vitro investigations. Am J Med 1989;87:89S-91S. PubMed
- Carbo M, Segura J, De la Torre R, et al. Effect of quinolones on caffeine disposition. Clin Pharmacol Ther 1989;45:234-40. PubMed
- Healy DP, Polk RE, Kanawati L, et al. Interaction between oral ciprofloxacin and caffeine in normal volunteers. Antimicrob Agents Chemother 1989;33:474-8. PubMed
- Mester R, Toren P, Mizrachi I, et al. Caffeine withdrawal increases lithium blood levels. Biol Psychiatry 1995;37:348-50. PubMed
- Jefferson JW. Lithium tremor and caffeine intake: two cases of drinking less and shaking more. J Clin Psychiatry 1988;49:72-3.
- Mitscher LA, Mitscher LA, Jung M, Shankel D, et al. Chemoprotection: a review of the potential therapeutic antioxidant properties of green tea (Camellia sinensis) and certain of its constituents. Med Res Rev 1997;17:327-65.
- Joeres R, Klinker H, Heusler H, et al. Influence of mexiletine on caffeine elimination. Pharmacol Ther 1987;33:163-9. PubMed
- Vahedi K, Domingo V, Amarenco P, Bousser MG. Ischemic stroke in a sportsman who consumed MaHuang extract and creatine monohydrate for bodybuilding. J Neurol Neurosurg Psychiatr 2000;68:112-3.
- Wakabayashi K, Kono S, Shinchi K, et al. Habitual coffee consumption and blood pressure: A study of self-defense officials in Japan. Eur J Epidemiol 1998;14:669-73. PubMed
- Hodgson JM, Puddey IB, Burke V, et al. Effects on blood pressure of drinking green and black tea. J Hypertens 1999;17:457-63. PubMed
- Booth SL, Madabushi HT, Davidson KW, et al. Tea and coffee brews are not dietary sources of vitamin K-1 (phylloquinone). J Am Diet Assoc 1995;95:82-3. PubMed
- Lou FQ, Zhang MF, Zhang XG, et al. A study on tea-pigment in prevention of atherosclerosis. Chin Med J (Engl) 1989;102:579-83.
- Graham HN. Green tea composition, consumption, and polyphenol chemistry. Prev Med 1992;21:334-50. PubMed
- Rapuri PB, Gallagher JC, Kinyamu HK, Ryschon KL. Caffeine intake increases the rate of bone loss in elderly women and interacts with vitamin D receptor genotypes. Am J Clin Nutr 2001;74:694-700. PubMed
- The National Toxicology Program (NTP). Caffeine. Center for the Evaluation of Risks to Human Reproduction (CERHR). Available at: http://cerhr.niehs.nih.gov/common/caffeine.html.
- Klebanoff MA, Levine RJ, DerSimonian R, et al. Maternal serum paraxanthine, a caffeine metabolite, and the risk of spontaneous abortion. N Engl J Med 1999;341:1639-44. PubMed
- Eskenazi B. Caffeine—filtering the facts. N Engl J Med 1999;341:1688-9. PubMed
- Fernandes O, Sabharwal M, Smiley T, et al. Moderate to heavy caffeine consumption during pregnancy and relationship to spontaneous abortion and abnormal fetal growth: a meta-analysis. Reprod Toxicol 1998;12:435-44. PubMed
- Pollock BG, Wylie M, Stack JA, et al. Inhibition of caffeine metabolism by estrogen replacement therapy in postmenopausal women. J Clin Pharmacol 1999;39:936-40. PubMed
- Dews PB, Curtis GL, Hanford KJ, O'Brien CP. The frequency of caffeine withdrawal in a population-based survey and in a controlled, blinded pilot experiment. J Clin Pharmacol 1999;39:1221-32. PubMed
- FDA. Proposed rule: dietary supplements containing ephedrine alkaloids. Available at: www.verity.fda.gov (Accessed 25 January 2000).
- Weisburger JH. Tea and health: the underlying mechanisms. Proc Soc Exp Biol Med 1999;220:271-5. PubMed
- Taylor JR, Wilt VM. Probable antagonism of warfarin by green tea. Ann Pharmacother 1999;33:426-8. PubMed
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Hagg S, Spigset O, Mjorndal T, Dahlqvist R. Effect of caffeine on clozapine pharmacokinetics in healthy volunteers. Br J Clin Pharmacol 2000;49:59-63. PubMed
- Watson JM, Jenkins EJ, Hamilton P, et al. Influence of caffeine on the frequency and perception of hypoglycemia in free-living patients with type 1 diabetes. Diabetes Care 2000;23:455-9. PubMed
- Lloyd T, Johnson-Rollings N, Eggli DF, et al. Bone status among postmenopausal women with different habitual caffeine intakes: a longitudinal investigation. J Am Coll Nutr 2000;19:256-61. PubMed
- American Academy of Pediatrics. The transfer of drugs and other chemicals into human milk. Pediatrics 2001;108:776-89. PubMed
- Heck AM, DeWitt BA, Lukes AL. Potential interactions between alternative therapies and warfarin. Am J Health Syst Pharm 2000;57:1221-7. DOI
- Sinclair CJ, Geiger JD. Caffeine use in sports. A pharmacological review. J Sports Med Phys Fitness 2000;40:71-9.
- Haller CA, Benowitz NL. Adverse cardiovascular and central nervous system events associated with dietary supplements containing ephedra alkaloids. N Engl J Med 2000;343:1833-8. PubMed
- Ali M, Afzal M. A potent inhibitor of thrombin stimulated platelet thromboxane formation from unprocessed tea. Prostaglandins Leukot Med 1987;27:9-13. PubMed
- Ardlie NG, Glew G, Schultz BG, Schwartz CJ. Inhibition and reversal of platelet aggregation by methyl xanthines. Thromb Diath Haemorrh 1967;18:670-3. DOI
- Ferrini RL, Barrett-Connor E. Caffeine intake and endogenous sex steroid levels in postmenopausal women. The Rancho Bernardo Study. Am J Epidemiol 1996:144:642-4. PubMed
- Pisters KM, Newman RA, Coldman B, et al. Phase I trial of oral green tea extract in adult patients with solid tumors. J Clin Oncol 2001;19:1830-8. PubMed
- Haller CA, Jacob P 3rd, Benowitz NL. Pharmacology of ephedra alkaloids and caffeine after single-dose dietary supplement use. Clin Pharmacol Ther 2002;71:421-32. PubMed
- Bell DG, Jacobs I, Ellerington K. Effect of caffeine and ephedrine ingestion on anaerobic exercise performance. Med Sci Sports Exerc 2001;33:1399-403. PubMed
- Horner NK, Lampe JW. Potential mechanisms of diet therapy for fibrocystic breast conditions show inadequate evidence of effectiveness. J Am Diet Assoc 2000;100:1368-80. PubMed
- Bracken MB, Triche EW, Belanger K, et al. Association of maternal caffeine consumption with decrements in fetal growth. Am J Epidemiol 2003;157:456-66.. PubMed
- McGowan JD, Altman RE, Kanto WP Jr. Neonatal withdrawal symptoms after chronic maternal ingestion of caffeine. South Med J 1988;81:1092-4.. PubMed
- Nehlig A, Debry G. Consequences on the newborn of chronic maternal consumption of coffee during gestation and lactation: a review. J Am Coll Nutr 1994;13:6-21.. PubMed
- Massey LK. Is caffeine a risk factor for bone loss in the elderly? Am J Clin Nutr 2001;74:569-70. PubMed
- Kockler DR, McCarthy MW, Lawson CL. Seizure activity and unresponsiveness after hydroxycut ingestion. Pharmacotherapy 2001;21:647-51.. PubMed
- Nix D, Zelenitsky S, Symonds W, et al. The effect of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. Clin Pharmacol Ther 1992;51:183. DOI
- Ahn WS, Yoo J, Huh SW, et al. Protective effects of green tea extracts (polyphenon E and EGCG) on human cervical lesions. Eur J Cancer Prev 2003;12:383-90. PubMed
- Infante S, Baeza ML, Calvo M, et al. Anaphylaxis due to caffeine. Allergy 2003;58:681-2. PubMed
- Massey LK, Whiting SJ. Caffeine, urinary calcium, calcium metabolism and bone. J Nutr 1993;123:1611-4. PubMed
- Shirai T, Hayakawa H, Akiyama J, et al. Food allergy to green tea. J Allergy Clin Immunol 2003;112:805-6. PubMed
- Jatoi A, Ellison N, Burch PA, et al. A phase II trial of green tea in the treatment of patients with androgen independent metastatic prostate carcinoma. Cancer 2003;97:1442-6.. PubMed
- Nawrot P, Jordan S, Eastwood J, et al. Effects of caffeine on human health. Food Addit Contam 2003;20:1-30. PubMed
- May DC, Jarboe CH, VanBakel AB, Williams WM. Effects of cimetidine on caffeine disposition in smokers and nonsmokers. Clin Pharmacol Ther 1982;31:656-61. PubMed
- Brown NJ, Ryder D, Branch RA. A pharmacodynamic interaction between caffeine and phenylpropanolamine. Clin Pharmacol Ther 1991;50:363-71. PubMed
- Sanderink GJ, Bournique B, Stevens J, et al. Involvement of human CYP1A isoenzymes in the metabolism and drug interactions of riluzole in vitro. Pharmacol Exp Ther 1997;282:1465-72. DOI
- Wahllander A, Paumgartner G. Effect of ketoconazole and terbinafine on the pharmacokinetics of caffeine in healthy volunteers. Eur J Clin Pharmacol 1989;37:279-83. PubMed
- Carrillo JA, Benitez J. Clinically significant pharmacokinetic interactions between dietary caffeine and medications. Clin Pharmacokinet 2000;39:127-53. PubMed
- Underwood DA. Which medications should be held before a pharmacologic or exercise stress test? Cleve Clin J Med 2002;69:449-50. PubMed
- Aqel RA, Zoghbi GJ, Trimm JR, et al. Effect of caffeine administered intravenously on intracoronary-administered adenosine-induced coronary hemodynamics in patients with coronary artery disease. Am J Cardiol 2004;93:343-6. PubMed
- Zheng XM, Williams RC. Serum caffeine levels after 24-hour abstention: clinical implications on dipyridamole (201)Tl myocardial perfusion imaging. J Nucl Med Technol 2002;30:123-7.
- Institute of Medicine. Caffeine for the Sustainment of Mental Task Performance: Formulations for Military Operations. Washington, DC: National Academy Press, 2001. Available at: http://books.nap.edu/books/0309082587/html/index.html. DOI
- Dews PB, O'Brien CP, Bergman J. Caffeine: behavioral effects of withdrawal and related issues. Food Chem Toxicol 2002;40:1257-61. PubMed
- Beach CA, Mays DC, Guiler RC, et al. Inhibition of elimination of caffeine by disulfiram in normal subjects and recovering alcoholics. Clin Pharmacol Ther 1986;39:265-70. PubMed
- Yang YC, Lu FH, Wu JS, et al. The protective effect of habitual tea consumption on hypertension. Arch Intern Med 2004 26;164:1534-40. PubMed
- Son DJ, Cho MR, Jin YR, et al. Antiplatelet effect of green tea catechins: a possible mechanism through arachidonic acid pathway. Prostaglandins Leukot Essent Fatty Acids 2004;71:25-31. PubMed
- Juliano LM, Griffiths RR. A critical review of caffeine withdrawal: empirical validation of symptoms and signs, incidence, severity, and associated features. Psychopharmacology (Berl) 2004;176:1-29. PubMed
- Winkelmayer WC, Stampfer MJ, Willett WC, Curhan GC. Habitual caffeine intake and the risk of hypertension in women. JAMA 2005;294:2330-5. PubMed
- Raaska K, Raitasuo V, Laitila J, Neuvonen PJ. Effect of caffeine-containing versus decaffeinated coffee on serum clozapine concentrations in hospitalised patients. Basic Clin Pharmacol Toxicol 2004;94:13-8. DOI
- Forrest WH Jr, Bellville JW, Brown BW Jr. The interaction of caffeine with pentobarbital as a nighttime hypnotic. Anesthesiology 1972;36:37-41. PubMed
- Lake CR, Rosenberg DB, Gallant S, et al. Phenylpropanolamine increases plasma caffeine levels. Clin Pharmacol Ther 1990;47:675-85. PubMed
- Bonkovsky HL. Hepatotoxicity associated with supplements containing Chinese green tea (Camellia sinensis). Ann Intern Med 2006;144:68-71.
- Gloro R, Hourmand-Ollivier I, Mosquet B, et al. Fulminant hepatitis during self-medication with hydroalcoholic extract of green tea. Eur J Gastroenterol Hepatol 2005;17:1135-7. PubMed
- Donovan JL, Chavin KD, Devane CL, et al. Green tea (Camellia sinensis) extract does not alter cytochrome P450 3A4 or 2D6 activity in healthy volunteers. Drug Metab Dispos 2004;32:906-8. PubMed
- Chu KO, Wang CC, Chu CY, et al. Pharmacokinetic studies of green tea catechins in maternal plasma and fetuses in rats. J Pharm Sci 2006;95:1372-81. PubMed
- Isbrucker RA, Edwards JA, Wolz E, et al. Safety studies on epigallocatechin gallate (EGCG) preparations. Part 3: teratogenicity and reproductive toxicity studies in rats. Food Chem Toxicol 2006;44:651-61. PubMed
- Navarro-Peran E, Cabezas-Herrera J, Garcia-Canovas F, et al. The antifolate activity of tea catechins. Cancer Res 2005;65:2059-64. PubMed
- Jimenez-Saenz M, Martinez-Sanchez, MDC. Acute hepatitis associated with the use of green tea infusions. J Hepatol 2006;44:616-9. PubMed
- Bradley Pharmaceuticals. Veregen Prescribing Information. October 2006.
- Correa A, Stolley A, Liu Y. Prenatal tea consumption and risks of anencephaly and spina bifida. Ann Epidemiol 2000;10:476-7. PubMed
- Weng X, Odouli R, Li DK. Maternal caffeine consumption during pregnancy and the risk of miscarriage: a prospective cohort study. Am J Obstet Gynecol 2008;198:279.e1-8. PubMed
- Savitz DA, Chan RL, Herring AH, et al. Caffeine and miscarriage risk. Epidemiology 2008;19:55-62. PubMed
- Golden ED, Lam PY, Kardosh A, et al. Green tea polyphenols block the anticancer effects of bortezomib and other boronic acid-based proteasome inhibitors. Blood 2009;113:5927-37. PubMed
- Misaka S, Yatabe J, Muller F, et al. Green Tea Ingestion Greatly Reduces Plasma Concentrations of Nadolol in Healthy Subjects. Clin Pharmacol Ther 2014. [Epub ahead of print]. PubMed
- Roth M, Timmermann BN, Hagenbuch B. Interactions of green tea catechins with organic anion-transporting polypeptides. Drug Metab Dispos 2011;39:920-6. PubMed
- Kato Y, Miyazaki T, Kano T, et al. Involvement of influx and efflux transport systems in gastrointestinal absorption of celiprolol. J Pharm Sci 2009;98:2529-39. PubMed
- Chan, H. T., So, L. T., Li, S. W., Siu, C. W., Lau, C. P., and Tse, H. F. Effect of herbal consumption on time in therapeutic range of warfarin therapy in patients with atrial fibrillation. J.Cardiovasc.Pharmacol. 2011;58(1):87-90. PubMed
- Nishikawa, M., Ariyoshi, N., Kotani, A., Ishii, I., Nakamura, H., Nakasa, H., Ida, M., Nakamura, H., Kimura, N., Kimura, M., Hasegawa, A., Kusu, F., Ohmori, S., Nakazawa, K., and Kitada, M. Effects of continuous ingestion of green tea or grape seed extrac
- Shet, M. S., McPhaul, M., Fisher, C. W., Stallings, N. R., and Estabrook, R. W. Metabolism of the antiandrogenic drug (Flutamide) by human CYP1A2. Drug Metab Dispos. 1997;25(11):1298-1303.
- Staib, A. H., Stille, W., Dietlein, G., Shah, P. M., Harder, S., Mieke, S., and Beer, C. Interaction between quinolones and caffeine. Drugs 1987;34 Suppl 1:170-174. PubMed
- Stille, W., Harder, S., Mieke, S., Beer, C., Shah, P. M., Frech, K., and Staib, A. H. Decrease of caffeine elimination in man during co-administration of 4-quinolones. J.Antimicrob.Chemother. 1987;20(5):729-734. PubMed
- Fuhr, U., Strobl, G., Manaut, F., Anders, E. M., Sorgel, F., Lopez-de-Brinas, E., Chu, D. T., Pernet, A. G., Mahr, G., Sanz, F., and . Quinolone antibacterial agents: relationship between structure and in vitro inhibition of the human cytochrome P450 isof
- Kot, M. and Daniel, W. A. Effect of diethyldithiocarbamate (DDC) and ticlopidine on CYP1A2 activity and caffeine metabolism: an in vitro comparative study with human cDNA-expressed CYP1A2 and liver microsomes. Pharmacol Rep. 2009;61(6):1216-1220. PubMed
- Gasior, M., Borowicz, K., Buszewicz, G., Kleinrok, Z., and Czuczwar, S. J. Anticonvulsant activity of phenobarbital and valproate against maximal electroshock in mice during chronic treatment with caffeine and caffeine discontinuation. Epilepsia 1996;37(3 PubMed
- Jankiewicz, K., Chroscinska-Krawczyk, M., Blaszczyk, B., and Czuczwar, S. J. [Caffeine and antiepileptic drugs: experimental and clinical data]. Przegl.Lek. 2007;64(11):965-967.
- Luszczki, J. J., Zuchora, M., Sawicka, K. M., Kozinska, J., and Czuczwar, S. J. Acute exposure to caffeine decreases the anticonvulsant action of ethosuximide, but not that of clonazepam, phenobarbital and valproate against pentetrazole-induced seizures i
- Chroscinska-Krawczyk, M., Jargiello-Baszak, M., Walek, M., Tylus, B., and Czuczwar, S. J. Caffeine and the anticonvulsant potency of antiepileptic drugs: experimental and clinical data. Pharmacol.Rep. 2011;63(1):12-18. PubMed
- Vaz, J., Kulkarni, C., David, J., and Joseph, T. Influence of caffeine on pharmacokinetic profile of sodium valproate and carbamazepine in normal human volunteers. Indian J.Exp.Biol. 1998;36(1):112-114.
- Gasior, M., Swiader, M., Przybylko, M., Borowicz, K., Turski, W. A., Kleinrok, Z., and Czuczwar, S. J. Felbamate demonstrates low propensity for interaction with methylxanthines and Ca2+ channel modulators against experimental seizures in mice. Eur.J Phar PubMed
- Mohiuddin, M., Azam, A. T., Amran, M. S., and Hossain, M. A. In vive effects of gliclazide and metformin on the plasma concentration of caffeine in healthy rats. Pak.J Biol Sci 5-1-2009;12(9):734-737.
- Mays, D. C., Camisa, C., Cheney, P., Pacula, C. M., Nawoot, S., and Gerber, N. Methoxsalen is a potent inhibitor of the metabolism of caffeine in humans. Clin.Pharmacol.Ther. 1987;42(6):621-626. PubMed
- Wojcikowski, J. and Daniel, W. A. Perazine at therapeutic drug concentrations inhibits human cytochrome P450 isoenzyme 1A2 (CYP1A2) and caffeine metabolism--an in vitro study. Pharmacol Rep. 2009;61(5):851-858. PubMed
- Daniel, W. A., Syrek, M., Rylko, Z., and Kot, M. Effects of phenothiazine neuroleptics on the rate of caffeine demethylation and hydroxylation in the rat liver. Pol.J Pharmacol 2001;53(6):615-621.
- Norager, C. B., Jensen, M. B., Weimann, A., and Madsen, M. R. Metabolic effects of caffeine ingestion and physical work in 75-year old citizens. A randomized, double-blind, placebo-controlled, cross-over study. Clin Endocrinol (Oxf) 2006;65(2):223-228. PubMed
- Wang, X. and Yeung, J. H. Effects of the aqueous extract from Salvia miltiorrhiza Bunge on caffeine pharmacokinetics and liver microsomal CYP1A2 activity in humans and rats. J Pharm Pharmacol 2010;62(8):1077-1083.
- Kot M, Daniel WA. Caffeine as a marker substrate for testing cytochrome P450 activity in human and rat. Pharmacol Rep 2008;60:789-97.
- Kjaerstad MB, Nielsen F, Nohr-Jensen L, et al. Systemic uptake of miconazole during vaginal suppository use and effect on CYP1A2 and CYP3A4 associated enzyme activities in women. Eur J Clin Pharmacol 2010;66:1189-97. PubMed
- Goh BC, Reddy NJ, Dandamudi UB, et al. An evaluation of the drug interaction potential of pazopanib, an oral vascular endothelial growth factor receptor tyrosine kinase inhibitor, using a modified Cooperstown 5+1 cocktail in patients with advanced solid t
- Chen Y, Kang Z, Yan J, et al. Liu wei di huang wan, a well-known traditional Chinese medicine induces CYP1A2 while suppressing CYP2A6 and N-acetyltransferase 2 acivities in man. J Ethnopharmacol 2010;132:213-8.
- Suzuki S, Murayama Y, Sugiyama E, et al. Estimating pediatric doses of drugs metabolized by cytochrome P450 (CYP) isozymes, based on physiological liver development and serum protein levels. Yakugaku Zasshi 2010;130:613-20. PubMed
- Chien CF, Wu YT, Lee WC, et al. Herb-drug interaction of Andrographis paniculata extract and andrographolide on the pharmacokinetics of theophylline in rats. Chem Biol Interact 2010;184:458-65. PubMed
- Mills BM, Zaya MJ, Walters RR, et al. Current cytochrome P450 phenotyping methods applied to metabolic drug -drug interaction prediction in dogs. Drug Metab Dispos 2010;38:396-404. PubMed
- Turpault S, Brian W, Van Horn R, et al. Pharmacokinetic assessment of a five-probe cocktail for CYPs 1A2, 2C9, 2C19, 2D6, and 3A. Br J Clin Pharmacol 2009;68:928-35. PubMed
- Filimonova AA, Ziganshina LE, Ziganshin AU, Chichirov AA. On the possibility of patient phenotyping on the basis of cytochrome p-450 1A2 isoenzyme activity using caffeine as the test substrate. Eksp Klin Farmakol 2009;72:61-5.
- Jenkins J, Williams D, Deng Y, et al. Eltrombopag, an oral thrombopoietin receptor agonist, has no impact on the pharmacokinetic profile of probe drugs for cytochrome P450 isoenzymes CYP3A4, CYP1A2, CYP2C9 and CYP2C19 in healthy men: a cocktail analysis.
- Chow, H. H., Cai, Y., Hakim, I. A., Crowell, J. A., Shahi, F., Brooks, C. A., Dorr, R. T., Hara, Y., and Alberts, D. S. Pharmacokinetics and safety of green tea polyphenols after multiple-dose administration of epigallocatechin gallate and polyphenon E i
- Gross, G., Meyer, K. G., Pres, H., Thielert, C., Tawfik, H., and Mescheder, A. A randomized, double-blind, four-arm parallel-group, placebo-controlled Phase II/III study to investigate the clinical efficacy of two galenic formulations of Polyphenon E in
- Stockfleth, E., Beti, H., Orasan, R., Grigorian, F., Mescheder, A., Tawfik, H., and Thielert, C. Topical Polyphenon E in the treatment of external genital and perianal warts: a randomized controlled trial. Br.J Dermatol. 2008;158(6):1329-1338.
- Smits, P., Temme, L., and Thien, T. The cardiovascular interaction between caffeine and nicotine in humans. Clin Pharmacol Ther 1993;54(2):194-204. PubMed
- MacKenzie, T., Comi, R., Sluss, P., Keisari, R., Manwar, S., Kim, J., Larson, R., and Baron, J. A. Metabolic and hormonal effects of caffeine: randomized, double-blind, placebo-controlled crossover trial. Metabolism 2007;56(12):1694-1698. PubMed
- Lopez-Garcia, E., Rodriguez-Artalejo, F., Rexrode, K. M., Logroscino, G., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of stroke in women. Circulation 3-3-2009;119(8):1116-1123. PubMed
- Zhang, W., Lopez-Garcia, E., Li, T. Y., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of cardiovascular diseases and all-cause mortality among men with type 2 diabetes. Diabetes Care 2009;32(6):1043-1045. PubMed
- Moisey, L. L., Robinson, L. E., and Graham, T. E. Consumption of caffeinated coffee and a high carbohydrate meal affects postprandial metabolism of a subsequent oral glucose tolerance test in young, healthy males. Br.J Nutr. 2010;103(6):833-841. PubMed
- Chroscinska-Krawczyk, M., Ratnaraj, N., Patsalos, P. N., and Czuczwar, S. J. Effect of caffeine on the anticonvulsant effects of oxcarbazepine, lamotrigine and tiagabine in a mouse model of generalized tonic-clonic seizures. Pharmacol Rep. 2009;61(5):819 PubMed
- Simmonds, M. J., Minahan, C. L., and Sabapathy, S. Caffeine improves supramaximal cycling but not the rate of anaerobic energy release. Eur.J Appl Physiol 2010;109(2):287-295. PubMed
- Buscemi, S., Verga, S., Batsis, J. A., Donatelli, M., Tranchina, M. R., Belmonte, S., Mattina, A., Re, A., and Cerasola, G. Acute effects of coffee on endothelial function in healthy subjects. Eur.J Clin Nutr. 2010;64(5):483-489. PubMed
- Rigato, I., Blarasin, L., and Kette, F. Severe hypokalemia in 2 young bicycle riders due to massive caffeine intake. Clin J Sport Med. 2010;20(2):128-130. PubMed
- Ernest, D., Chia, M., and Corallo, C. E. Profound hypokalaemia due to Nurofen Plus and Red Bull misuse. Crit Care Resusc. 2010;12(2):109-110. DOI
- Conen, D., Chiuve, S. E., Everett, B. M., Zhang, S. M., Buring, J. E., and Albert, C. M. Caffeine consumption and incident atrial fibrillation in women. Am J Clin Nutr 2010;92(3):509-514. PubMed
- Reis, J. P., Loria, C. M., Steffen, L. M., Zhou, X., van, Horn L., Siscovick, D. S., Jacobs, D. R., Jr., and Carr, J. J. Coffee, decaffeinated coffee, caffeine, and tea consumption in young adulthood and atherosclerosis later in life: the CARDIA study. A PubMed
- Clausen, T. Hormonal and pharmacological modification of plasma potassium homeostasis. Fundam.Clin Pharmacol 2010;24(5):595-605. PubMed
- Gronroos, N. N. and Alonso, A. Diet and risk of atrial fibrillation - epidemiologic and clinical evidence -. Circ.J 2010;74(10):2029-2038. PubMed
- Perera, V., Gross, A. S., and McLachlan, A. J. Caffeine and paraxanthine HPLC assay for CYP1A2 phenotype assessment using saliva and plasma. Biomed.Chromatogr. 2010;24(10):1136-1144. PubMed
- Orozco-Gregorio, H., Mota-Rojas, D., Bonilla-Jaime, H., Trujillo-Ortega, M. E., Becerril-Herrera, M., Hernandez-Gonzalez, R., and Villanueva-Garcia, D. Effects of administration of caffeine on metabolic variables in neonatal pigs with peripartum asphyxia PubMed
- Izzo, A. A. and Ernst, E. Interactions between herbal medicines and prescribed drugs: an updated systematic review. Drugs 2009;69(13):1777-1798. PubMed
- Laurie, S. A., Miller, V. A., Grant, S. C., Kris, M. G., and Ng, K. K. Phase I study of green tea extract in patients with advanced lung cancer. Cancer Chemother.Pharmacol. 2005;55(1):33-38. PubMed
- Chiu, A. E., Chan, J. L., Kern, D. G., Kohler, S., Rehmus, W. E., and Kimball, A. B. Double-blinded, placebo-controlled trial of green tea extracts in the clinical and histologic appearance of photoaging skin. Dermatol Surg. 2005;31(7 Pt 2):855-860. PubMed
- Javaid, A. and Bonkovsky, H. L. Hepatotoxicity due to extracts of Chinese green tea (Camellia sinensis): a growing concern. J Hepatol 2006;45(2):334-335. PubMed
- Martinez-Sierra, C., Rendon, Unceta P., and Martin, Herrera L. [Acute hepatitis after green tea ingestion]. Med Clin (Barc.) 6-17-2006;127(3):119.
- Molinari, M., Watt, K. D., Kruszyna, T., Nelson, R., Walsh, M., Huang, W. Y., Nashan, B., and Peltekian, K. Acute liver failure induced by green tea extracts: case report and review of the literature. Liver Transpl. 2006;12(12):1892-1895. PubMed
- Chow, H. H., Hakim, I. A., Vining, D. R., Crowell, J. A., Cordova, C. A., Chew, W. M., Xu, M. J., Hsu, C. H., Ranger-Moore, J., and Alberts, D. S. Effects of repeated green tea catechin administration on human cytochrome P450 activity. Cancer Epidemiol.B PubMed
- Federico, A., Tiso, A., and Loguercio, C. A case of hepatotoxicity caused by green tea. Free Radic.Biol Med 8-1-2007;43(3):474. PubMed
- Sarma, D. N., Barrett, M. L., Chavez, M. L., Gardiner, P., Ko, R., Mahady, G. B., Marles, R. J., Pellicore, L. S., Giancaspro, G. I., and Low, Dog T. Safety of green tea extracts : a systematic review by the US Pharmacopeia. Drug Saf 2008;31(6):469-484. PubMed
- Engdal, S. and Nilsen, O. G. In vitro inhibition of CYP3A4 by herbal remedies frequently used by cancer patients. Phytother.Res. 2009;23(7):906-912.
- Bergman, J. and Schjott, J. Hepatitis caused by Lotus-f3? Basic Clin Pharmacol.Toxicol. 2009;104(5):414-416. PubMed
- Kalus, U., Kiesewetter, H., and Radtke, H. Effect of CYSTUS052 and green tea on subjective symptoms in patients with infection of the upper respiratory tract. Phytother.Res. 2010;24(1):96-100.
- Tatti, S., Stockfleth, E., Beutner, K. R., Tawfik, H., Elsasser, U., Weyrauch, P., and Mescheder, A. Polyphenon E: a new treatment for external anogenital warts. Br.J Dermatol. 2010;162(1):176-184.
- Tsao, A. S., Liu, D., Martin, J., Tang, X. M., Lee, J. J., El-Naggar, A. K., Wistuba, I., Culotta, K. S., Mao, L., Gillenwater, A., Sagesaka, Y. M., Hong, W. K., and Papadimitrakopoulou, V. Phase II randomized, placebo-controlled trial of green tea extra
- Liatsos, G. D., Moulakakis, A., Ketikoglou, I., and Klonari, S. Possible green tea-induced thrombotic thrombocytopenic purpura. Am.J Health Syst.Pharm. 4-1-2010;67(7):531-534. PubMed
- Josic, J., Olsson, A. T., Wickeberg, J., Lindstedt, S., and Hlebowicz, J. Does green tea affect postprandial glucose, insulin and satiety in healthy subjects: a randomized controlled trial. Nutr.J. 2010;9:63. PubMed
- Miller, R. J., Jackson, K. G., Dadd, T., Mayes, A. E., Brown, A. L., and Minihane, A. M. The impact of the catechol-O-methyltransferase genotype on the acute responsiveness of vascular reactivity to a green tea extract. Br.J.Nutr. 2011;105(8):1138-1144.
- Rohde, J., Jacobsen, C., and Kromann-Andersen, H. [Toxic hepatitis triggered by green tea]. Ugeskr.Laeger 1-17-2011;173(3):205-206.
- Tzellos, T. G., Sardeli, C., Lallas, A., Papazisis, G., Chourdakis, M., and Kouvelas, D. Efficacy, safety and tolerability of green tea catechins in the treatment of external anogenital warts: a systematic review and meta-analysis. J.Eur.Acad.Dermatol.Ve PubMed
- Otera, H., Tada, K., Sakurai, T., Hashimoto, K., and Ikeda, A. Hypersensitivity pneumonitis associated with inhalation of catechin-rich green tea extracts. Respiration 2011;82(4):388-392. PubMed
- Yellapu, R. K., Mittal, V., Grewal, P., Fiel, M., and Schiano, T. Acute liver failure caused by 'fat burners' and dietary supplements: a case report and literature review. Can.J.Gastroenterol. 2011;25(3):157-160. PubMed
- Karth, A., Holoshitz, N., Kavinsky, C. J., Trohman, R., and McBride, B. F. A case report of atrial fibrillation potentially induced by hydroxycut: a multicomponent dietary weight loss supplement devoid of sympathomimetic amines. J.Pharm.Pract. 2010;23(3) PubMed
- Hsu, C. H., Liao, Y. L., Lin, S. C., Tsai, T. H., Huang, C. J., and Chou, P. Does supplementation with green tea extract improve insulin resistance in obese type 2 diabetics? A randomized, double-blind, and placebo-controlled clinical trial. Altern.Med.R
- Zheng XX, Xu YL, Li SH, et al. Green tea intake lowers fasting serum total and LDL cholesterol in adults: a meta-analysis of 14 randomized controlled trials. Am.J.Clin.Nutr. 2011;94:601-610. PubMed
- Miller, R. J., Jackson, K. G., Dadd, T., Mayes, A. E., Brown, A. L., Lovegrove, J. A., and Minihane, A. M. The impact of the catechol-O-methyltransferase genotype on vascular function and blood pressure after acute green tea ingestion. Mol.Nutr.Food Res.
- Bogdanski, P., Suliburska, J., Szulinska, M., Stepien, M., Pupek-Musialik, D., and Jablecka, A. Green tea extract reduces blood pressure, inflammatory biomarkers, and oxidative stress and improves parameters associated with insulin resistance in obese, h
- Jurgens, T. M., Whelan, A. M., Killian, L., Doucette, S., Kirk, S., and Foy, E. Green tea for weight loss and weight maintenance in overweight or obese adults. Cochrane.Database.Syst.Rev. 2012;12:CD008650. PubMed
- Sakamoto, O., Saita, N., Yamasaki, H., Tamanoi, M., and Ando, M. Pulmonary granulomatosis caused by aspirated green tea. Chest 1994;106(1):308-309. PubMed
- Jiménez-Encarnación E, Ríos G, Muñoz-Mirabal A, Vilá LM. Euforia-induced acute hepatitis in a patient with scleroderma. BMJ Case Rep 2012;2012. PubMed
- Choi JS, Burm JP. Effects of oral epigallocatechin gallate on the pharmacokinetics of nicardipine in rats. Arch Pharm Res. 2009 Dec;32(12):1721-5. PubMed
- Chung JH, Choi DH, Choi JS. Effects of oral epigallocatechin gallate on the oral pharmacokinetics of verapamil in rats. Biopharm Drug Dispos. 2009 Mar;30(2):90-3. PubMed
- Crew KD, Brown P, Greenlee H, Bevers TB, Arun B, Hudis C, McArthur HL, Chang J, Rimawi M, Vornik L, Cornelison TL, Wang A, Hibshoosh H, Ahmed A, Terry MB, Santella RM, Lippman SM, Hershman DL. Phase IB randomized, double-blinded, placebo-controlled, dose
- Dryden GW, Lam A, Beatty K, Qazzaz HH, McClain CJ. A pilot study to evaluate the safety and efficacy of an oral dose of (-)-epigallocatechin-3-gallate-rich polyphenon E in patients with mild to moderate ulcerative colitis. Inflamm Bowel Dis. 2013 Aug;19(9 PubMed
- Gallo E, Maggini V, Berardi M, Pugi A, Notaro R, Talini G, Vannozzi G, Bagnoli S, Forte P, Mugelli A, Annese V, Firenzuoli F, Vannacci A. Is green tea a potential trigger for autoimmune hepatitis? Phytomedicine. 2013 Oct 15;20(13):1186-9. PubMed
- Liu K, Zhou R, Wang B, Chen K, Shi LY, Zhu JD, Mi MT. Effect of green tea on glucose control and insulin sensitivity: a meta-analysis of 17 randomized controlled trials. Am J Clin Nutr. 2013 Aug;98(2):340-8. PubMed
- Onakpoya I, Spencer E, Heneghan C, Thompson M. The effect of green tea on blood pressure and lipid profile: a systematic review and meta-analysis of randomized clinical trials. Nutr Metab Cardiovasc Dis. 2014 Aug;24:823-36. PubMed
- Patel SS, Beer S, Kearney DL, Phillips G, Carter BA. Green tea extract: a potential cause of acute liver failure. World J Gastroenterol. 2013 Aug 21;19(31):5174-7. PubMed
- Pillukat MH, Bester C, Hensel A, Lechtenberg M, Petereit F, Beckebaum S, Müller KM, Schmidt HH. Concentrated green tea extract induces severe acute hepatitis in a 63-year-old woman--a case report with pharmaceutical analysis. J Ethnopharmacol. 2014 Aug 8; PubMed
- Schönthal AH. Adverse effects of concentrated green tea extracts. Mol Nutr Food Res. 2011 Jun;55(6):874-85. PubMed
- Shiraishi M, Haruna M, Matsuzaki M, Ota E, Murayama R, Murashima S. Association between the serum folate levels and tea consumption during pregnancy. Biosci Trends. 2010 Oct;4(5):225-30.
- Jang EH, Choi JY, Park CS, Lee SK, Kim CE, Park HJ, Kang JS, Lee JW, Kang JH. Effects of green tea extract administration on the pharmacokinetics of clozapine in rats. J Pharm Pharmacol. 2005 Mar;57(3):311-6. PubMed
- Trudel D, Labbé DP, Araya-Farias M, Doyen A, Bazinet L, Duchesne T, Plante M, Grégoire J, Renaud MC, Bachvarov D, Têtu B, Bairati I. A two-stage, single-arm, phase II study of EGCG-enriched green tea drink as a maintenance therapy in women with advanced s
- Zheng XX, Xu YL, Li SH, Hui R, Wu YJ, Huang XH. Effects of green tea catechins with or without caffeine on glycemic control in adults: a meta-analysis of randomized controlled trials. Am J Clin Nutr. 2013 Apr;97(4):750-62. PubMed
- Caldeira D, Martins C, Alves LB, Pereira H, Ferreira JJ, Costa J. Caffeine does not increase the risk of atrial fibrillation: a systematic review and meta-analysis of observational studies. Heart. 2013;99(19):1383-9. doi: 10.1136/heartjnl-2013-303950. Re PubMed
- Cheng M, Hu Z, Lu X, Huang J, Gu D. Caffeine intake and atrial fibrillation incidence: dose response meta-analysis of prospective cohort studies. Can J Cardiol. 2014 Apr;30(4):448-54. doi: 10.1016/j.cjca.2013.12.026. Epub 2014 2. Review. PubMed
- van der Hoeven N, Visser I, Schene A, van den Born BJ. Severe hypertension related to caffeinated coffee and tranylcypromine: a case report. Ann Intern Med. 2014 May 6;160(9):657-8. doi: 10.7326/L14-5009-8. No abstract available. PubMed
- Dixit S, Stein PK, Dewland TA, Dukes JW, Vittinghoff E, Heckbert SR, Marcus GM. Consumption of Caffeinated Products and Cardiac Ectopy. J Am Heart Assoc. 2016 26;5(1). pii: e002503. doi: 10.1161/JAHA.115.002503. PubMed
- Health Canada. Health Product Info Watch. October 2016; 5-6. Available at: http://www.hc-sc.gc.ca/dhp-mps/medeff/bulletin/hpiw-ivps_2016-10-eng.php#a15.
- Green Tea Extract-Containing Natural Health Products - Rare Risk of Serious Liver Injury. Recalls & alerts. November 15, 2017. http://healthycanadians.gc.ca/recall-alert-rappel-avis/hc-sc/2017/65100a-eng.php. Accessed November 10, 2017.
- Mazzanti G, Di Sotto A, Vitalone A. Hepatotoxicity of green tea: an update. Arch Toxicol. 2015;89(8):1175-91. PubMed
- Isomura T, Suzuki S, Origasa H, et al. Liver-related safety assessment of green tea extracts in humans: a systematic review of randomized controlled trials. Eur J Clin Nutr. 2016;70(11):1221-1229. PubMed
- Drug Record: Green Tea (Camellia Sinesis). LiverTox: National Institutes of Health, U.S. Department of Health & Human Services, March 2014. https://livertox.nlm.nih.gov//GreenTea.htm. Accessed November 20, 2017.
- Yates AA, Erdman JW Jr, Shao A, Dolan LC, Griffiths JC. Bioactive nutrients - Time for tolerable upper intake levels to address safety. Regul Toxicol Pharmacol. 2017;84:94-101. PubMed
- Younes M, Aggett P, Aguilar F, et al. EFSA Panel on Food Additives and Nutrient Sources added to Food (ANS). Scientific opinion on the safety of green tea catechins. EFSA Journal 2018;16(4):5239. PubMed
- Zuchinali P, Riberio PA, Pimentel M, da Rosa PR, Zimerman LI, Rohde LE. Effect of caffeine on ventricular arrhythmia: a systematic review and meta-analysis of experimental and clinical studies. Europace 2016 Feb;18(2):257-66. PubMed
- Dostal AM, Samavat H, Bedell S, et al. The safety of green tea extract supplementation in postmenopausal women at risk for breast cancer: results of the Minnesota Green Tea Trial. Food Chem Toxicol. 2015 Sep;83:26-35. PubMed
- Shamekhi Z, Amani R, Habibagahi Z, Namjoyan F, Ghadiri A, Saki Malehi A. A Randomized, Double-blind, Placebo-controlled Clinical Trial Examining the Effects of Green Tea Extract on Systemic Lupus Erythematosus Disease Activity and Quality of Life. Phytoth PubMed
- Lagier D, Nee L, Guieu R, et al. Peri-operative oral caffeine does not prevent postoperative atrial fibrillation after heart valve surgery with cardiopulmonary bypass: a randomized controlled clinical trial. Eur J Anaesthesiol. 2018 Apr 26. [Epub ahead of DOI
- Voskoboinik A, Kalman JM, Kistler PM. Caffeine and arrhythmias: time to grind the data. JACC: Clin Electrophysiol. 2018;4(4):425-32. PubMed
- Chong SJ, Howard KA, Knox C. Hypokalaemia and drinking green tea: a literature review and report of 2 cases. BMJ Case Rep. 2016;2016. pii: bcr2016214425. PubMed
- Qiao J, Gu C, Shang W, et al. Effect of green tea on pharmacokinetics of 5-fluorouracil in rats and pharmacodynamics in human cell lines in vitro. Food Chem Toxicol. 2011;49(6):1410-5. PubMed
- Abe O, Ono T, Sato H, et al. Role of (-)-epigallocatechin gallate in the pharmacokinetic interaction between nadolol and green tea in healthy volunteers. Eur J Clin Pharmacol 2018;74(6):775-83. doi: 10.1007/s00228-018-2436-2. PubMed
- Wikoff D, Welsh BT, Henderson R, et al. Systematic review of the potential adverse effects of caffeine consumption in healthy adults, pregnant women, adolescents, and children. Food Chem Toxicol 2017;109:585-648. PubMed
- Nutescu EA, Shapiro NL, Ibrahim S, et al. Warfarin and its interactions with foods, herbs and other dietary supplements. Expert Opin Drug Saf. 2006;5(3):433-51. PubMed
- Abdelkawy KS, Abdelaziz RM, Abdelmageed AM, Donia AM, El-Khodary NM. Effects of green tea extract on atorvastatin pharmacokinetics in healthy volunteers. Eur J Drug Metab Pharmacokinet. 2020;45(3):351-360. PubMed
- Filippini T, Malavolti M, Borrelli F, et al. Green tea (Camellia sinensis) for the prevention of cancer. Cochrane Database Syst Rev. 2020;3(3):CD005004. PubMed
- Huang S, Xu Q, Liu L, et al. Effect of green tea and (-)-epigallocatechin gallate on the pharmacokinetics of rosuvastatin. Curr Drug Metab. 2020. PubMed
- Mahmoodi M, Hosseini R, Kazemi A, Ofori-Asenso R, Mazidi M, Mazloomi SM. Effects of green tea or green tea catechin on liver enzymes in healthy individuals and people with nonalcoholic fatty liver disease: A systematic review and meta-analysis of randomiz
- Misaka S, Abe O, Ono T, et al. Effects of single green tea ingestion on pharmacokinetics of nadolol in healthy volunteers. Br J Clin Pharmacol. 2020. PubMed
- Oketch-Rabah HA, Roe AL, Rider CV, et al. United States Pharmacopeia (USP) comprehensive review of the hepatotoxicity of green tea extracts. Toxicol Rep. 2020;7:386-402. PubMed
- Kim TE, Ha N, Kim Y, et al. Effect of epigallocatechin-3-gallate, major ingredient of green tea, on the pharmacokinetics of rosuvastatin in healthy volunteers. Drug Des Devel Ther. 2017;11:1409-1416. PubMed
- Misaka S, Ono Y, Uchida A, et al. Impact of green tea catechin ingestion on the pharmacokinetics of lisinopril in healthy volunteers. Clin Transl Sci. 2020. PubMed
- Darweesh RS, El-Elimat T, Zayed A, et al. The effect of grape seed and green tea extracts on the pharmacokinetics of imatinib and its main metabolite, N-desmethyl imatinib, in rats. BMC Pharmacol Toxicol. 2020;21(1):77. PubMed
- Sonoda J, Ogata K, Yoshikawa N, Sato K, Ikeda R, Shimodozono Y. Impact of green tea intake on the pharmacokinetics of celiprolol in healthy subjects. Int J Clin Pharmacol Ther. 2020. PubMed
- Kim S, Park TH, Kim WI, Park S, Kim JH, Cho MK. The effects of green tea on acne vulgaris: A systematic review and meta-analysis of randomized clinical trials. Phytother Res. 2021;35(1):374-383. PubMed
- Percevault S, Charpiat B, Lebossé F, Mabrut JY, Vial T, Colom M. Green tea and hepatoxicity: Two case reports. Therapie 2021. PubMed
- Kajita N, Miyama S, Kinoshita K, Yoshida K, Narita M. Green tea-induced anaphylaxis: The first pediatric case report. Allergol Int 2021;70(4):507-508. PubMed
- Zheng KH, Zhu K, Wactawski-Wende J, et al. Caffeine intake from coffee and tea and invasive breast cancer incidence among postmenopausal women in the Women's Health Initiative. Int J Cancer 2021;149(12):2032-2044. PubMed
- Wang S, Li X, Yang Y, et al. Does coffee, tea and caffeine consumption reduce the risk of incident breast cancer? A systematic review and network meta-analysis. Public Health Nutr 2021;24(18):6377-6389. PubMed
- Alshabi AM, Alkahtani SA, Shaikh IA, Habeeb MS. Caffeine modulates pharmacokinetic and pharmacodynamic profiles of pioglitazone in diabetic rats: Impact on therapeutics. Saudi Med J 2021;42(2):151-160. PubMed
- Gleason JL, Sundaram R, Mitro SD, et al. Association of maternal caffeine consumption during pregnancy with child growth. JAMA Netw Open. 2022;5(10):e2239609. PubMed
- Seufferlein T, Ettrich TJ, Menzler S, et al. Green tea extract to prevent colorectal adenomas, results of a randomized, placebo-controlled clinical trial. Am J Gastroenterol 2022;117(6):884-894. PubMed
- Teramoto M, Yamagishi K, Muraki I, Tamakoshi A, Iso H. Coffee and green tea consumption and cardiovascular disease mortality among people with and without hypertension. J Am Heart Assoc 2023;12(2):e026477. PubMed
- Veerman GDM, van der Werff SC, Koolen SLW, et al. The influence of green tea extract on nintedanib's bioavailability in patients with pulmonary fibrosis. Biomed Pharmacother 2022;151:113101. PubMed
- Misaka S, Ono Y, Taudte RV, et al. Exposure of fexofenadine, but not pseudoephedrine, is markedly decreased by green tea extract in healthy volunteers. Clin Pharmacol Ther 2022;112(3):627-634. PubMed
- Zhao H, Zhu W, Zhao X, et al. Efficacy of epigallocatechin-3-gallate in preventing dermatitis in patients with breast cancer receiving postoperative radiotherapy: A double-blind, placebo-controlled, phase 2 randomized clinical trial. JAMA Dermatol 2022;15 PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
Ashwagandha 32 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Upton R, ed. Ashwagandha Root (Withania somnifera): Analytical, quality control, and therapuetic monograph. Santa Cruz, CA: American Herbal Pharmacopoeia 2000:1-25.
- Davis L, Kuttan G. Effect of Withania somnifera on cyclophosphamide-induced urotoxicity. Cancer Lett 2000;148:9-17. PubMed
- Davis L, Kuttan G. Suppressive effect of cyclophosphamide-induced toxicity by Withania somnifera extract in mice. J Ethnopharmacol 1998;62:209-14. PubMed
- Mishra LC, Singh BB, Dagenais S. Scientific basis for the therapeutic use of Withania somnifera (ashwagandha): a review. Altern Med Rev 2000;5:334-46. DOI
- Andallu B, Radhika B. Hypoglycemic, diuretic and hypocholesterolemic effect of winter cherry (Withania somnifera, Dunal) root. Indian J Exp Biol 2000;38:607-9.
- Kulkarni RR, Patki PS, Jog VP, et al. Treatment of osteoarthritis with a herbomineral formulation: a double-blind, placebo-controlled, cross-over study. J Ethnopharmacol 1991;33:91-5. PubMed
- Ahumada F, Aspee F, Wikman G, Hancke J. Withania somnifera exract. Its effects on arterial blood pressure in anaesthetized dogs. Phytother Res 1991;5:111-14.
- Panda S, Kar A. Withania somnifera and Bauhinia purpurea in the regulation of circulating thyroid hormone concentrations in female mice. J Ethnopharmacol 1999;67:233-39. PubMed
- Panda S, Kar A. Changes in thyroid hormone concentrations after administration of ashwagandha root extract to adult male mice. J Pharm Pharmacol 1998;50:1065-68. PubMed
- Sehgal, V. N., Verma, P., and Bhattacharya, S. N. Fixed-drug eruption caused by ashwagandha (Withania somnifera): a widely used Ayurvedic drug. Skinmed. 2012;10(1):48-49.
- Agnihotri AP, Sontakke SD, Thawani VR, Saoji A, Goswami VS. Effects of Withania somnifera in patients of schizophrenia: a randomized, double blind, placebo controlled pilot trial study. Indian J Pharmacol. 2013;45(4):417-8. PubMed
- Biswal BM, Sulaiman SA, Ismail HC, Zakaria H, Musa KI. Effect of Withania somnifera (Ashwagandha) on the development of chemotherapy-induced fatigue and quality of life in breast cancer patients. Integr Cancer Ther. 2013;12(4):312-22.
- Sharma AK, Basu I, Singh S. Efficacy and safety of Ashwagandha root extract in subclinical hypothyroid patients: a double-blind, randomized placebo-controlled trial. J Altern Complement Med. 2018 Mar;24(3):243-248. PubMed
- Durg S, Bavage S, Shivaram SB. Withania somnifera (Indian ginseng) in diabetes mellitus: A systematic review and meta-analysis of scientific evidence from experimental research to clinical application. Phytother Res. 2020;34(5):1041-1059.
- Björnsson HK, Björnsson ES, Avula B, et al. Ashwagandha-induced liver injury: A case series from Iceland and the US Drug-Induced Liver Injury Network. Liver Int. 2020;40(4):825-829. PubMed
- Tharakan A, Shukla H, Benny IR, Tharakan M, George L, Koshy S. Immunomodulatory Effect of Withania somnifera (Ashwagandha) Extract-A Randomized, Double-Blind, Placebo Controlled Trial with an Open Label Extension on Healthy Participants. J Clin Med 2021;1 PubMed
- Ireland PJ, Hardy T, Burt AD, Donnelly MC. Drug-induced hepatocellular injury due to herbal supplement ashwagandha. J R Coll Physicians Edinb. 2021;51(4):363-365. PubMed
- Kamal HI, Patel K, Brdak A, Heffernan J, Ahmad N. Ashwagandha as a unique cause of thyrotoxicosis presenting with supraventricular tachycardia. Cureus. 2022 Mar 25;14(3):e23494. PubMed
- Suryawanshi G, Abdallah M, Thomson M, Desai N, Chauhan A, Lim N. Ashwagandha-Associated Acute Liver Failure Requiring Liver Transplantation. Am J Ther 2023;30(1):e80-e83. PubMed
- Pusec CM, Wolsky R, Llerena C, Sura P. A Case of Supplement-Induced Hepatitis. Cureus 2022;14(10):e30433. PubMed
- Ajgaonkar A, Jain M, Debnath K. Efficacy and Safety of Ashwagandha (Withania somnifera) Root Extract for Improvement of Sexual Health in Healthy Women: A Prospective, Randomized, Placebo-Controlled Study. Cureus 2022;14(10):e30787. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Lubarska M, Halasinski P, Hryhorowicz S, et al. Liver Dangers of Herbal Products: A Case Report of Ashwagandha-Induced Liver Injury. Int J Environ Res Public Health 2023;20(5):3921. PubMed
- Tóth M, Benedek AE, Longerich T, Seitz HK. Ashwagandha-induced acute liver injury: A case report. Clin Case Rep 2023;11(3):e7078.
- Bokan G, Glamocanin T, Mavija Z, et al. Herb-Induced Liver Injury by Ayurvedic Ashwagandha as Assessed for Causality by the Updated RUCAM: An Emerging Cause. Pharmaceuticals (Basel) 2023;16(8):1129. PubMed
- Patel PA, Sanborn E, Then R, Williams DM. Recurrent Reversible Cerebral Vasoconstriction Syndrome: A Report of Two Cases. Cureus 2023;15(8):e42992. PubMed
- Majeed M, Nagabhushanam K, Murali A, Vishwanathan DT, Mamidala RV, Mundkur L. A Standardized Withania somniferra (Linn.) Root Extract with Piperine Alleviates the Symptoms of Anxiety and Depression by Increasing Serotonin Levels: A Double-Blind, Randomize
- Philips CA, Valsan A, Theruvath AH, et al. Ashwagandha-induced liver injury-A case series from India and literature review. Hepatol Commun 2023;7(10):e0270. PubMed
- Hayashi M, Hamada H, Azuma SI, Hayashi K. Painless Thyroiditis by Withania somnifera (Ashwagandha). Cureus 2024;16(3):e55352. PubMed
- Vazirani S, Kothari A, Fujimoto J, Gomez M. Supplements Are Not a Synonym for Safe: Suspected Liver Injury From Ashwagandha. Fed Pract 2023;40(9):315-319. PubMed
- Patel M, Newell R, Hillier M, Ramalingam R. Herbal remedies as a potential cause of hypoadrenalism. Br J Hosp Med (Lond) 2024;85(6):1-4. PubMed
Sage 27 references
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
- Todorov S, Philianos S, Petkov V, et al. Experimental pharmacological study of three species from genus Salvia. Acta Physiol Pharmacol (Bulg) 1984;10:13-20.
- Perry NS, Bollen C, Perry EK, Ballard C. Salvia for dementia therapy: review of pharmacological activity and pilot tolerability clinical trial. Pharmacol Biochem Behav 2003;75:651-9.. PubMed
- Saller R, Buechi S, Meyrat R, Schmidhauser C. Combined herbal preparation for topical treatment of Herpes labialis. Forsch Komplementarmed Klass Naturheilkd 2001;8:373-82. PubMed
- Akhondzadeh S, Noroozian M, Mohammadi M, et al. Salvia officinalis extract in the treatment of patients with mild to moderate Alzheimer's disease: a double blind, randomized and placebo-controlled trial. J Clin Pharm Ther 2003;28:53-9.
- Perry NB, Anderson RE, Brennan NJ, et al. Essential oils from dalmatian sage (Salvia officinalis l.): variations among individuals, plant parts, seasons, and sites. J Agric Food Chem 1999;47:2048-54..
- Foster BC, Vandenhoek S, Hana J, et al. In vitro inhibition of human cytochrome P450-mediated metabolism of marker substrates by natural products. Phytomedicine 2003;10:334-42.. PubMed
- Burkhard PR, Burkhardt K, Haenggeli CA, Landis T. Plant-induced seizures: reappearance of an old problem. J Neurol 1999;246:667-70. PubMed
- Bommer S, Klein P, Suter A. First time proof of sage's tolerability and efficacy in menopausal women with hot flushes. Adv Ther 2011;28:490-500. PubMed
- Hellum BH, Nilsen OG. The in vitro inhibitory potential of trade herbal products on human CYP2D6-mediated metabolism and the influence of ethanol. Basic Clin Pharmacol Toxicol. 2007 Nov;101:350-8.
- Orhan, I., Kartal, M., Kan, Y., and Sener, B. Activity of essential oils and individual components against acetyl- and butyrylcholinesterase. Z.Naturforsch.C. 2008;63(7-8):547-553.
- Perry, N. S., Houghton, P. J., Theobald, A., Jenner, P., and Perry, E. K. In-vitro inhibition of human erythrocyte acetylcholinesterase by salvia lavandulaefolia essential oil and constituent terpenes. J Pharm Pharmacol 2000;52(7):895-902.
- Perry, N. S., Houghton, P. J., Sampson, J., Theobald, A. E., Hart, S., Lis-Balchin, M., Hoult, J. R., Evans, P., Jenner, P., Milligan, S., and Perry, E. K. In-vitro activity of S. lavandulaefolia (Spanish sage) relevant to treatment of Alzheimer's diseas
- Futrell, J. M. and Rietschel, R. L. Spice allergy evaluated by results of patch tests. Cutis 1993;52(5):288-290.
- Kavvadias, D., Monschein, V., Sand, P., Riederer, P., and Schreier, P. Constituents of sage (Salvia officinalis) with in vitro affinity to human brain benzodiazepine receptor. Planta Med. 2003;69(2):113-117.
- Savelev, S. U., Okello, E. J., and Perry, E. K. Butyryl- and acetyl-cholinesterase inhibitory activities in essential oils of Salvia species and their constituents. Phytother Res 2004;18(4):315-324.
- Kennedy, D. O., Pace, S., Haskell, C., Okello, E. J., Milne, A., and Scholey, A. B. Effects of cholinesterase inhibiting sage (Salvia officinalis) on mood, anxiety and performance on a psychological stressor battery. Neuropsychopharmacology 2006;31(4):84 PubMed
- Hubbert, M., Sievers, H., Lehnfeld, R., and Kehrl, W. Efficacy and tolerability of a spray with Salvia officinalis in the treatment of acute pharyngitis - a randomised, double-blind, placebo-controlled study with adaptive design and interim analysis. Eur
- Lima, C. F., Fernandes-Ferreira, M., and Pereira-Wilson, C. Drinking of Salvia officinalis tea increases CCl(4)-induced hepatotoxicity in mice. Food Chem.Toxicol. 2007;45(3):456-464.
- Hellum, B. H. and Nilsen, O. G. In vitro inhibition of CYP3A4 metabolism and P-glycoprotein-mediated transport by trade herbal products. Basic Clin Pharmacol Toxicol. 2008;102(5):466-475.
- Mayer, E., Gescheidt-Shoshany, H., and Weltfriend, S. Allergic contact dermatitis caused by Salvia officinalis extract. Contact Dermatitis 2011;64(4):237-238. PubMed
- Halicioglu, O., Astarcioglu, G., Yaprak, I., and Aydinlioglu, H. Toxicity of Salvia officinalis in a newborn and a child: an alarming report. Pediatr.Neurol. 2011;45(4):259-260. PubMed
- Sertoli, A., Fabbri, P., Campolmi, P., and Panconesi, E. Allergic contact dermatitis to Salvia Officinalis, Inula Viscosa and Conyza Bonariensis. Contact Dermatitis 1978;4(5):314-315.
- Vandecasteele K, Ost P, Oosterlinck W, et al. Evaluation of the efficacy and safety of Salvia officinalis in controlling hot flashes in prostate cancer patients treated with androgen deprivation. Phytother Res. 2012;26(2):208-13.
- Kianbakht S, Dabaghian FH. Improved glycemic control and lipid profile in hyperlipidemic type 2 diabetic patients consuming Salvia officinalis L. leaf extract: a randomized placebo. Controlled clinical trial. Complement Ther Med. 2013;21(5):441-6. PubMed
- Amini L, Mojab F, Jahanfar S, Sepidarkish M, Raoofi Z, Maleki-Hajiagha A. Efficacy of Salvia officinalis extract on the prevention of insulin resistance in euglycemic patients with polycystic ovary syndrome: A double-blinded placebo-controlled clinical tr
- Behradmanesh S, Derees F, Rafieian-Kopaei M. Effect of Salvia officinalis on diabetic patients. J Renal Inj Prev. 2013;2(2):51-4.
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC