
Alive Cola Ingredients & Drug Interactions
by GT’s Alive
What is this page for?
First and foremost: checking Alive Cola against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Alive Cola is a dietary supplement by GT’s Alive with 10 active ingredients. Its ingredients are commonly taken for replacing fluids and electrolytes, preventing dehydration during exercise or illness, treating low blood sodium (under medical care).Based on those ingredients, 2,208 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Dietary Fiber, Caffeine, Reishi Mushroom. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Alive Cola by GT’s Alive
Ask about any prescription or over-the-counter medication and we check it for interactions with Alive Cola by GT’s Alive — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Alive Cola by GT’s Alive
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Partial disclosure
GT's Alive Cola contains 8 active ingredients. The product provides sodium and vitamin C for their roles in nutrition and immune support.
It also contains four medicinal mushrooms — reishi, chaga, turkey tail, and one listed only as "Blend" — along with caffeine and apple cider vinegar. The remaining listed ingredients are excipients and flavoring agents (black tea, apple juice, lime juice, cinnamon, erythritol, cane sugar, vanilla extract, kola nut, sea salt, black pepper, and stevia).
Does it work?
Strong evidence
Sodium is rated Likely Effective for cystic fibrosis and Possibly Effective for amphotericin B kidney damage; evidence is insufficient to rate it for bipolar disorder or congestive heart failure. Vitamin C is rated Effective for vitamin C deficiency and Possibly Effective for anemia of chronic disease, atrial fibrillation, cataracts, and exercise-related respiratory infections.
Caffeine is rated Effective for neonatal apnea and postoperative headache, and Likely Effective for mental alertness and athletic performance. Reishi mushroom, chaga, and turkey tail mushroom all carry insufficient evidence to rate them for most conditions; reishi is rated Possibly Ineffective for high cholesterol, and turkey tail is rated Possibly Effective for cancer.
Apple cider vinegar has insufficient evidence for the conditions we hold data on — acne, athletic performance, cognitive function, dental plaque, depression, and eczema.
How safe is it?
Well-documented data
Sodium is generally well tolerated at normal dietary amounts, but too much is linked to high blood pressure and heart strain; avoid sodium supplements or very high intake without medical advice. Vitamin C is generally well tolerated and considered likely safe in pregnancy and lactation at normal amounts, though very high doses can cause side effects including abdominal cramps, diarrhea, nausea, and kidney stones in those prone to them.
Caffeine in moderate amounts is typically well tolerated in healthy adults, though high doses can cause anxiety, insomnia, tremors, and rarely stroke; safety data in pregnancy are not on file, so discuss intake limits with your doctor, and small amounts pass into breast milk. Reishi mushroom is generally well tolerated short-term but long-term safety is not well studied; safety data advise against use in pregnancy and breastfeeding.
Chaga and turkey tail mushroom are generally used in foods and teas but have limited human safety data; chaga carries a rare risk of kidney failure from excessive consumption due to high oxalate content, and both are advised against in pregnancy and breastfeeding. Apple cider vinegar is well tolerated in food amounts but can cause harm in undiluted or large doses; long-term large-dose use has been associated with dangerously low potassium, high renin levels, and bone loss.
Meds to double-check
Major interaction found
Before taking GT's Alive Cola, double-check with your pharmacist if you take ephedrine (Major severity risk of serious stimulant side effects), or any Moderate-severity interactions: blood pressure medications, corticosteroids, lithium, oral contraceptives or hormone therapy, blood thinners or anticoagulants, warfarin, chemotherapy drugs, digoxin, diuretics, insulin, diabetes drugs, levothyroxine, or the antipsychotic fluphenazine. No interactions are documented for erythritol, the only ingredient we could not check.
The bottom line
Scorecard at a glancePartially disclosed formula with clinical evidence supporting its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
GT's Alive Cola is a caffeinated supplement blend suitable for those seeking general wellness from mushrooms and vitamin C without medication interactions — but it carries significant interactions if you take blood pressure drugs, blood thinners, oral contraceptives, or diabetes medications. If you're on any prescription medication, especially ephedrine, lithium, warfarin, estrogen-based birth control, thyroid replacement, or blood sugar drugs, check your exact medications with the search tool before use.
Talk to your pharmacist or doctor about whether this product is right for you.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 8 of 9 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jun 25, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Alive Cola, straight from the product label.
| Brand | GT’s Alive |
|---|---|
| Net contents | 16 Fluid Ounce(s); 473 mL |
| Market status | On market |
| Date entered into DSLD | Jun 25, 2025 |
| DSLD ID | 333659 |
| Product type | Other Combinations |
| Supplement form | Liquid |
| Dietary claims / uses | Nutrient, All Other |
| Intended target group(s) | Adult (18 - 50 Years) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
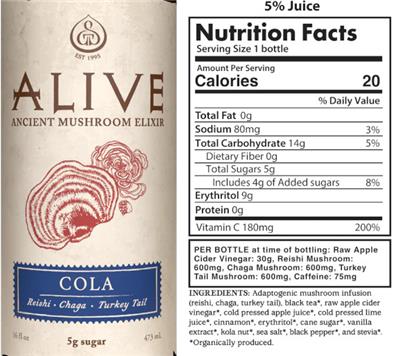
Supplement Facts
The label details for Alive Cola by GT’s Alive, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Calories | 20 Calorie(s) | -- |
| Total Carbohydrates | 14 Gram(s) | 5% |
| Sodium | 80 mg | 3% |
| Vitamin C | 180 mg | 200% |
| Added Sugars | 4 Gram(s) | 8% |
| Total Sugars | 5 Gram(s) | -- |
| Total Fat | 0 Gram(s) | -- |
| Dietary Fiber | 0 Gram(s) | -- |
| Protein | 0 Gram(s) | -- |
| Blend | 0 NP | -- |
| Reishi Mushroom | 600 mg | -- |
| Erythritol | 9 Gram(s) | -- |
| Caffeine | 75 mg | -- |
| Chaga Mushroom | 600 mg | -- |
| Apple Cider Vinegar, Raw | 30 Gram(s) | -- |
| Turkey Tail Mushroom | 600 mg | -- |
Other ingredients: Reishi, Chaga, Turkey Tail, Black Tea, Apple Juice, Cold Pressed, Lime Juice, Cold Pressed, Cinnamon, Erythritol, Cane Sugar, Vanilla extract, Kola Nut, Sea Salt, Black Pepper, Stevia
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Brand IP Statement(s)
GT's Alive Est 1995
Formulation
Ancient Mushroom Elixir
Formula
Reishi Chaga Turkey Tail 5 g Sugar 5% Juice Per bottle at time of bottling: Raw Apple Cider Vinegar: 30 g, Reishi Mushroom: 600 mg, Chaga Mushroom: 600 mg, Turkey Tail Mushroom: 600 mg, Caffeine: 75 mg
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Alive Cola by GT’s Alive label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Alive Cola by GT’s Alive
These are the 10 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Bottle(s) Dosage formLiquid Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Sodium
Interacts with205 drugs
Sodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets g...
Sodium monograph & interactionsVitamin C
Interacts with207 drugs
Vitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for im...
Vitamin C monograph & interactionsDietary Fiber
Interacts with2,025 drugs
Black psyllium is a soluble-fiber supplement made from the seeds of a Plantago plant, used mostly to ease constipation and support digestive health. I...
Dietary Fiber monograph & interactionsProtein
Blend
Erythritol
Other (inactive) ingredients: Reishi, Chaga, Turkey Tail, Black Tea, Apple Juice, Cold Pressed, Lime Juice, Cold Pressed, Cinnamon, Erythritol, Cane Sugar, Vanilla extract, Kola Nut, Sea Salt, Black Pepper, Stevia. These complete the product’s ingredient list but are not active constituents.
Alive Cola by GT’s Alive Drug Interactions
HelloPharmacist Interaction Report
GT's Alive Cola contains several ingredients with documented interactions with medications.
The most serious concern is caffeine, which carries a Major severity interaction with ephedrine — concomitant use can increase the risk of serious, life-threatening stimulant adverse effects including dangerously high blood pressure and heart problems.
Read the full breakdown — every affected drug type, severity by severity
Sodium in this product interacts with multiple drug types at Moderate severity: blood pressure medications (antihypertensives), corticosteroids, lithium, certain HIV antivirals like didanosine, bowel-prep sodium phosphates, and the vasopressin antagonist tolvaptan. The main risks are reduced blood pressure control, increased salt retention leading to high sodium levels (hypernatremia), and altered lithium levels including potential toxicity.
Vitamin C has Moderate interactions with oral estrogens (including hormonal contraceptives — up to 55% increase in estrogen levels), certain chemotherapy drugs, warfarin (a blood thinner), the antipsychotic fluphenazine, the HIV drug indinavir, levothyroxine (thyroid replacement), and aluminum supplements. Additionally, reishi mushroom, chaga, and turkey tail mushroom each carry Moderate interactions with blood sugar medications and blood thinners or anticoagulants.
Apple cider vinegar interacts with diuretics, digoxin (a heart medication), insulin, and diabetes drugs. Erythritol could not be checked — we hold no data for it.
Additionally, use of the search tool below to check your exact medications is strongly recommended before starting this product. Altogether, these interactions span 1,001 individual medications.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Alive Cola?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Alive Cola interact with 2,208 drugs. Click any drug to see the details.
8 of the 10 ingredients in Alive Cola interact with drugs. Each result below shows which ingredient is responsible. Dietary Fiber Caffeine Reishi Mushroom Chaga Mushroom Vitamin C Sodium Turkey Tail Mushroom Apple Cider Vinegar, Raw
Aminophylline, Amobarbital, EphedrineAmesec
How Aminophylline, Amobarbital, Ephedrine interacts with Alive Cola — through 2 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs, Ephedrine Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Aminophylline, Amobarbital, Ephedrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Aminophylline, Amobarbital, Ephedrine interactionCarbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine TannateQuadratuss, Ry Tuss, Rynatuss, Tri Tannate Plus
How Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interacts with Alive Cola — through 2 ingredients. Tap an ingredient for the detail:
CaffeineEphedrine, Stimulant Drugs Major
Interaction Summary
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Read the full Caffeine + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionDyphylline, Ephedrine, Guaifenesin, PhenobarbitalLufyllin-EPG
How Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interacts with Alive Cola — through 2 ingredients. Tap an ingredient for the detail:
CaffeinePhenobarbital (luminal), Ephedrine +1 Major
Interaction Summary
Theoretically, caffeine might reduce the effects of phenobarbital and increase the risk for convulsions.
Read the full Caffeine + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionEphedrine, Guaifenesin (otc Drug)Ephedrine Formula 400, Ephedrine Plus Tabs
How Ephedrine, Guaifenesin (otc Drug) interacts with Alive Cola — through 2 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs, Ephedrine Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Ephedrine, Guaifenesin (otc Drug) interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Ephedrine, Guaifenesin (otc Drug) interactionEphedrine, Guaifenesin, Phenobarbital, TheophyllineMudrane GG
How Ephedrine, Guaifenesin, Phenobarbital, Theophylline interacts with Alive Cola — through 2 ingredients. Tap an ingredient for the detail:
CaffeineTheophylline, Phenobarbital (luminal) +2 Major
Interaction Summary
Theoretically, caffeine might increase the levels and adverse effects of theophylline.
Read the full Caffeine + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionEphedrine, Hydroxyzine, TheophyllineAmi Rax, Marax
How Ephedrine, Hydroxyzine, Theophylline interacts with Alive Cola — through 2 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs, Theophylline +1 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Ephedrine, Hydroxyzine, Theophylline interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Ephedrine, Hydroxyzine, Theophylline interactionEphedrine, Phenobarbital, Potassium Iodide, TheophyllineMudrane, Quadrinal
How Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interacts with Alive Cola — through 2 ingredients. Tap an ingredient for the detail:
CaffeineTheophylline, Phenobarbital (luminal) +2 Major
Interaction Summary
Theoretically, caffeine might increase the levels and adverse effects of theophylline.
Read the full Caffeine + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionEphedrine, Phenobarbital, TheophyllineTedral
How Ephedrine, Phenobarbital, Theophylline interacts with Alive Cola — through 2 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs, Theophylline +2 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Ephedrine, Phenobarbital, Theophylline interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Ephedrine, Phenobarbital, Theophylline interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with Alive Cola — through 2 ingredients. Tap an ingredient for the detail:
Chaga MushroomImmunosuppressants Moderate
Interaction Summary
Theoretically, chaga might interfere with immunosuppressive therapy.
Read the full Chaga Mushroom + 6-mercaptopurine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + 6-mercaptopurine interactionAbciximabReoPro
How Abciximab interacts with Alive Cola — through 4 ingredients. Tap an ingredient for the detail:
Chaga MushroomAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, chaga may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Chaga Mushroom + Abciximab interactionReishi MushroomAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, high doses of reishi mushroom might increase the risk of bleeding.
Read the full Reishi Mushroom + Abciximab interactionCaffeineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, caffeine may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Caffeine + Abciximab interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Abciximab interactionAbrocitinibCibinqo
How Abrocitinib interacts with Alive Cola — through 5 ingredients. Tap an ingredient for the detail:
Reishi MushroomAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, high doses of reishi mushroom might increase the risk of bleeding.
Read the full Reishi Mushroom + Abrocitinib interactionCaffeineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, caffeine may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Caffeine + Abrocitinib interactionChaga MushroomAnticoagulant/antiplatelet Drugs, Immunosuppressants Moderate
Interaction Summary
Theoretically, chaga may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Chaga Mushroom + Abrocitinib interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Abrocitinib interactionTurkey Tail MushroomCytochrome P450 2c9 (cyp2c9) Substrates Minor
Interaction Summary
Theoretically, the polysaccharide peptide (PSP) component of turkey tail mushroom might inhibit CYP2C9.
Read the full Turkey Tail Mushroom + Abrocitinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Alive Cola — through 6 ingredients. Tap an ingredient for the detail:
Chaga MushroomAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking chaga with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Chaga Mushroom + Acarbose interactionTurkey Tail MushroomAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking turkey tail mushroom with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Turkey Tail Mushroom + Acarbose interactionReishi MushroomAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, reishi mushroom might have additive effects with antidiabetes drugs.
Read the full Reishi Mushroom + Acarbose interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acarbose interactionApple Cider Vinegar, RawAntidiabetes Drugs Minor
Interaction Summary
Theoretically, taking apple cider vinegar with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Apple Cider Vinegar, Raw + Acarbose interactionCaffeineAntidiabetes Drugs Minor
Interaction Summary
Theoretically, taking caffeine with antidiabetes drugs might interfere with blood glucose control.
Read the full Caffeine + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Alive Cola — through 3 ingredients. Tap an ingredient for the detail:
Reishi MushroomAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, concurrent use of reishi mushroom with antihypertensive drugs might increase the risk of hypotension.
Read the full Reishi Mushroom + Acebutolol interactionSodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Acebutolol interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Alive Cola — through 4 ingredients. Tap an ingredient for the detail:
Chaga MushroomAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, chaga may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Chaga Mushroom + Acenocoumarol interactionCaffeineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, caffeine may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Caffeine + Acenocoumarol interactionReishi MushroomAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, high doses of reishi mushroom might increase the risk of bleeding.
Read the full Reishi Mushroom + Acenocoumarol interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acenocoumarol interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with Alive Cola — through 5 ingredients. Tap an ingredient for the detail:
Chaga MushroomAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, chaga may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Chaga Mushroom + Acetaminophen, Aspirin interactionReishi MushroomAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, high doses of reishi mushroom might increase the risk of bleeding.
Read the full Reishi Mushroom + Acetaminophen, Aspirin interactionCaffeineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, caffeine may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Caffeine + Acetaminophen, Aspirin interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Aspirin interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with Alive Cola — through 5 ingredients. Tap an ingredient for the detail:
CaffeineAnticoagulant/antiplatelet Drugs, Stimulant Drugs Moderate
Interaction Summary
Theoretically, caffeine may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Caffeine + Acetaminophen, Aspirin, Caffeine interactionReishi MushroomAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, high doses of reishi mushroom might increase the risk of bleeding.
Read the full Reishi Mushroom + Acetaminophen, Aspirin, Caffeine interactionChaga MushroomAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, chaga may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Chaga Mushroom + Acetaminophen, Aspirin, Caffeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Aspirin, Caffeine interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with Alive Cola — through 3 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs, Phenylpropanolamine Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with Alive Cola — through 3 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Butalbital, Caffeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with Alive Cola — through 3 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Butalbital, Caffeine, Codeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with Alive Cola — through 3 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with Alive Cola — through 3 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Caffeine, Codeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with Alive Cola — through 3 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Caffeine, Codeine, Salicylamide interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine, Salicylamide interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with Alive Cola — through 3 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Caffeine, Dihydrocodeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Dihydrocodeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Caffeine, IsomethepteneMigralam
How Acetaminophen, Caffeine, Isometheptene interacts with Alive Cola — through 3 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Caffeine, Isometheptene interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Isometheptene interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Isometheptene interactionAcetaminophen, Caffeine, PyrilamineMidol Max Strength Menstrual
How Acetaminophen, Caffeine, Pyrilamine interacts with Alive Cola — through 4 ingredients. Tap an ingredient for the detail:
Apple Cider Vinegar, RawDiuretic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of apple cider vinegar with diuretic drugs might increase the risk of hypokalemia.
Read the full Apple Cider Vinegar, Raw + Acetaminophen, Caffeine, Pyrilamine interactionCaffeineDiuretic Drugs, Stimulant Drugs Moderate
Interaction Summary
Theoretically, using caffeine with diuretic drugs might increase the risk of hypokalemia.
Read the full Caffeine + Acetaminophen, Caffeine, Pyrilamine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Caffeine, Pyrilamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Pyrilamine interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with Alive Cola — through 3 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionAcetaminophen, Chlorpheniramine, Dextromethorphan, PhenylpropanolamineMulti Symptom Cold Relief
How Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interacts with Alive Cola — through 3 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs, Phenylpropanolamine Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionAcetaminophen, Chlorpheniramine, Dextromethorphan, PseudoephedrineChildren's Tylenol Cold Plus Cough, Tylenol Cold Ex Strength
How Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interacts with Alive Cola — through 3 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interactionAcetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, SalicylamideRhinogesic GG
How Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interacts with Alive Cola — through 3 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interactionAcetaminophen, Chlorpheniramine, PhenylephrineAlka-Seltzer PLUS, Histex SR, Protid
How Acetaminophen, Chlorpheniramine, Phenylephrine interacts with Alive Cola — through 3 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Chlorpheniramine, Phenylephrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorpheniramine, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Phenylephrine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Alive Cola with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Dietary Fiber
Carbamazepine (Tegretol)
Theoretically, black psyllium might reduce the effects of carbamazepine and increase the risk for convulsions.
Theoretically, black psyllium might reduce carbamazepine absorption. A preliminary study using blond psyllium reported decreased carbamazepine bioavailability due to binding of the drug to psyllium, as well as reduction of available fluid in the gut for dissolution of the drug. This interaction may also occur with black psyllium.
Lithium
Theoretically, taking black psyllium at the same time as lithium might reduce lithium absorption.
The fiber in black psyllium might reduce lithium absorption and plasma levels. Some case reports describe a reduction in plasma lithium levels with concomitant administration of blond psyllium. This was reversed when psyllium was stopped. This interaction may also occur with black psyllium.
Metformin (Glucophage)
Theoretically, black psyllium might increase the therapeutic and adverse effects of metformin.
Animal research shows that concurrent consumption of blond psyllium with metformin slows and increases the absorption of metformin. This interaction may also occur with black psyllium. To avoid changes in absorption, take psyllium 30-60 minutes after metformin.
Olanzapine (Zyprexa)
Theoretically, taking black psyllium at the same time as olanzapine might reduce olanzapine absorption.
The fiber in black psyllium might decrease the absorption of olanzapine. A single case report describes a reduction in the effectiveness of olanzapine when it was concomitantly administered with an unspecified type of psyllium 3 grams orally twice daily. This effect was reversed when psyllium was stopped.
Digoxin (Lanoxin)
Theoretically, taking black psyllium at the same time as digoxin might reduce digoxin absorption and decrease digoxin levels.
Psyllium might bind digoxin in the gut. However, some clinical evidence suggests that psyllium does not impact digoxin absorption.
Ethinyl Estradiol
Theoretically, taking black psyllium at the same time as ethinyl estradiol might alter levels of estradiol.
Concurrent use of blond psyllium with ethinyl estradiol results in a slight increase in the extent of ethinyl estradiol absorption and a slower rate of absorption. This is unlikely to be clinically significant.
Oral Drugs
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Psyllium seems to have variable effects on drug absorption. To avoid changes in absorption, take psyllium 30-60 minutes after oral medications. Animal research shows that blond psyllium delays and increases the absorption of metformin and ethinyl estradiol. Case reports and animal research suggest that blond psyllium might reduce absorption of lithium, digoxin, olanzapine, and carbamazepine. Finally, some pharmacokinetic studies show that psyllium does not affect the absorption of levothyroxine or warfarin. Although many of these studies evaluated blond psyllium, the fiber content in black psyllium may have similar effects.
Caffeine
Ephedrine
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Use of ephedrine with caffeine can increase the risk of stimulatory adverse effects. There is evidence that using ephedrine with caffeine might increase the risk of serious life-threatening or debilitating adverse effects such as hypertension, myocardial infarction, stroke, seizures, and death.
Adenosine (Adenocard)
Theoretically, caffeine might decrease the vasodilatory effects of adenosine and interfere with its use prior to stress testing.
Some evidence shows that caffeine is a competitive inhibitor of adenosine and can reduce the vasodilatory effects of adenosine in humans. However, other research shows that caffeine does not seem to affect supplemental adenosine because high interstitial levels of adenosine overcome the antagonistic effects of caffeine. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. However, methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Anticoagulant/Antiplatelet Drugs
Theoretically, caffeine may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Caffeine is reported to have antiplatelet activity. Theoretically, it might increase the risk of bleeding when used concomitantly with these agents; however, this interaction has not been reported in humans.
Beta-Adrenergic Agonists
Theoretically, large amounts of caffeine might increase the cardiac inotropic effects of beta-agonists.
Carbamazepine (Tegretol)
Theoretically, caffeine might reduce the effects of carbamazepine and increase the risk for convulsions.
Animal research suggests that taking caffeine can lower the anticonvulsant effects of carbamazepine and can induce seizures when taken in doses above 400 mg/kg. Human research has shown that taking caffeine 300 mg in three divided doses along with carbamazepine 200 mg reduces the bioavailability of carbamazepine by 32% and prolongs the plasma half-life of carbamazepine 2-fold in healthy individuals.
Cimetidine (Tagamet)
Theoretically, cimetidine might increase the levels and adverse effects of caffeine.
Cimetidine decreases the rate of caffeine clearance by 31% to 42%.
Clozapine (Clozaril)
Caffeine might increase the levels and adverse effects of clozapine and acutely exacerbate psychotic symptoms.
Caffeine might increase the effects and toxicity of clozapine. Caffeine doses of 400-1000 mg per day inhibit clozapine metabolism. Clozapine is metabolized by cytochrome P450 1A2 (CYP1A2). Although researchers speculate that caffeine might inhibit CYP1A2, there is no reliable evidence that caffeine affects CYP1A2. There is also speculation that genetic factors might make some patients more sensitive to an interaction between clozapine and caffeine. In one case report, severe, life-threatening clozapine toxicity and multiorgan system failure occurred in a patient with schizophrenia stabilized on clozapine who consumed caffeine 600 mg daily.
Dipyridamole (Persantine)
Theoretically, caffeine might decrease the vasodilatory effects of dipyridamole and interfere with its use prior to stress testing.
Caffeine inhibits dipyridamole-induced vasodilation. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. Methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Disulfiram (Antabuse)
Theoretically, disulfiram use might increase the levels and adverse effects of caffeine.
Disulfiram decreases the rate of caffeine clearance.
Diuretic Drugs
Theoretically, using caffeine with diuretic drugs might increase the risk of hypokalemia.
Caffeine, especially in excessive amounts, can reduce potassium levels due to stimulation of the sodium-potassium pump. Diuretics can also cause lower potassium levels.
Estrogens
Theoretically, estrogens might increase the levels and adverse effects of caffeine.
Estrogen inhibits caffeine metabolism.
Ethosuximide (Zarontin)
Theoretically, caffeine might reduce the effects of ethosuximide and increase the risk for convulsions.
Animal research suggests that caffeine 92.4 mg/kg can decrease the anticonvulsant activity of ethosuximide. However, this effect has not been reported in humans.
Felbamate (Felbatol)
Theoretically, caffeine might reduce the effects of felbamate and increase the risk for convulsions.
Animal research suggests that a high dose of caffeine 161.7 mg/kg can decreases the anticonvulsant activity of felbamate. However, this effect has not been reported in humans.
Flutamide (Eulexin)
Theoretically, caffeine might increase the levels and adverse effects of flutamide.
In vitro evidence suggests that caffeine can inhibit the metabolism of flutamide. However, this effect has not been reported in humans.
Fluvoxamine (Luvox)
Theoretically, fluvoxamine might increase the levels and adverse effects of caffeine.
Fluvoxamine reduces caffeine metabolism.
Lithium
Abrupt caffeine withdrawal might increase the levels and adverse effects of lithium.
Caffeine has diuretic activity. When abruptly discontinued, caffeine may alter the clearance of lithium. There are two case reports of lithium tremor that worsened upon abrupt coffee withdrawal and 6 case reports of elevated serum lithium levels after reducing or eliminating caffeine intake. In one case, a male with schizoaffective disorder stabilized on lithium had an elevated lithium level after reducing his caffeine intake by 87%. At a later date, he increased his caffeine intake by 6-fold, resulting in a subtherapeutic lithium level and a recurrence of psychiatric symptoms.
Monoamine Oxidase Inhibitors (Maois)
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Caffeine has been shown to inhibit monoamine oxidase (MAO) A and B in laboratory studies. Concomitant intake of large amounts of caffeine with MAOIs might precipitate a hypertensive crisis. In a case report, a patient that consumed 10-12 cups of caffeinated coffee and took the MAOI tranylcypromine presented with severe hypertension. Hypertension was resolved after the patient switched to drinking decaffeinated coffee.
Nicotine
Theoretically, concomitant use might increase the risk of hypertension.
Concomitant use of caffeine and nicotine has been shown to have additive cardiovascular effects, including increased heart rate and blood pressure. Blood pressure was increased by 10.8/12.4 mmHg when the agents were used concomitantly.
Pentobarbital (Nembutal)
Theoretically, caffeine might decrease the effects of pentobarbital.
Caffeine might negate the hypnotic effects of pentobarbital.
Phenobarbital (Luminal)
Theoretically, caffeine might reduce the effects of phenobarbital and increase the risk for convulsions.
Animal research suggests that caffeine can decrease the anticonvulsant activity of phenobarbital. However, the exact mechanism of this interaction is unclear.
Phenylpropanolamine
Theoretically, phenylpropanolamine might increase the risk of hypertension, as well as the levels and adverse effects of caffeine.
Concomitant use of phenylpropanolamine and caffeine might cause an additive increase in blood pressure. Phenylpropanolamine also seems to increase caffeine serum levels.
Phenytoin (Dilantin)
Theoretically, caffeine might reduce the effects of phenytoin and increase the risk for convulsions.
Animal research suggests that caffeine can decrease the anticonvulsant activity of phenytoin. The effect does not seem to be related to the seizure threshold-lowering effects of caffeine. However, the exact mechanism of this interaction is unclear.
Pioglitazone (Actos)
Theoretically, caffeine might increase the levels and clinical effects of pioglitazone.
Animal research suggests that caffeine can modestly increase the maximum concentration, area under the curve, and half-life of pioglitazone, and also reduce its clearance. This increased the antidiabetic effects of pioglitazone. However, the exact mechanism of this interaction is unclear.
Quinolone Antibiotics
Theoretically, quinolone antibiotics might increase the levels and adverse effects of caffeine.
Quinolones (also called fluoroquinolones) can decrease caffeine clearance by inhibiting cytochrome P450 1A2 (CYP1A2) enzyme.
Riluzole (Rilutek)
Theoretically, concomitant use might increase the levels and adverse effects of both caffeine and riluzole.
Caffeine and riluzole are both metabolized by cytochrome P450 1A2 (CYP1A2), and concomitant use might reduce the metabolism of one or both agents.
Reishi Mushroom
Anticoagulant/Antiplatelet Drugs
Theoretically, high doses of reishi mushroom might increase the risk of bleeding.
A dose of 1.5 grams daily of reishi mushroom does not seem to decrease platelet aggregation, but a higher dose of 3 grams daily does.
Antidiabetes Drugs
Theoretically, reishi mushroom might have additive effects with antidiabetes drugs.
Animal research suggests that reishi mushroom decreases blood sugar. However, in patients with type 2 diabetes, taking reishi mushroom does not reduce fasting glucose levels, and its effects on glycated hemoglobin are inconsistent.
Antihypertensive Drugs
Theoretically, concurrent use of reishi mushroom with antihypertensive drugs might increase the risk of hypotension.
Reishi mushroom has shown hypotensive activity in animal research. Clinical evidence suggests that reishi mushroom reduces blood pressure in some, but not all, patients with hypertension.
Chaga Mushroom
Anticoagulant/Antiplatelet Drugs
Theoretically, chaga may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro and animal research suggests that chaga extract can inhibit platelet aggregation. This effect has not been reported in humans.
Antidiabetes Drugs
Theoretically, taking chaga with antidiabetes drugs might increase the risk of hypoglycemia.
Animal research suggests that chaga might decrease blood glucose levels and increase insulin levels. This has not been reported in humans.
Immunosuppressants
Theoretically, chaga might interfere with immunosuppressive therapy.
In vitro research suggests that certain constituents of chaga stimulate immune function. This has not been reported in humans.
Vitamin C
Alkylating Agents
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin C have on chemotherapy.
Aluminum
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Research in animals and humans shows that vitamin C increases aluminum absorption, theoretically by chelating aluminum and keeping it in solution where it is available for absorption. In people with normal renal function, urinary excretion of aluminum will likely increase, making aluminum retention and toxicity unlikely. Patients with renal failure who take aluminum-containing compounds such as phosphate binders should avoid vitamin C supplements in doses above the recommended dietary allowances.
Antitumor Antibiotics
Theoretically, the antioxidant effects of vitamin C might reduce the effectiveness of antitumor antibiotics.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as doxorubicin. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effects, if any, antioxidants such as vitamin C have on chemotherapy.
Estrogens
Vitamin C might increase blood levels of estrogens.
Increases in plasma estrogen levels of up to 55% occur under some circumstances when vitamin C is taken concurrently with oral contraceptives or hormone replacement therapy, including topical products. It is suggested that vitamin C prevents oxidation of estrogen in the tissues, regenerates oxidized estrogen, and reduces sulfate conjugation of estrogen in the gut wall. When tissue levels of vitamin C are high, these processes are already maximized and supplemental vitamin C does not have any effect on estrogen levels. Increases in plasma estrogen levels may occur when patients who are deficient in vitamin C take supplements. Monitor these patients for estrogen-related side effects.
Fluphenazine (Prolixin)
Theoretically, vitamin C might decrease levels of fluphenazine.
In one patient there was a clinically significant decrease in fluphenazine levels when vitamin C (500 mg twice daily) was started. The mechanism is not known, and there is no further data to confirm this interaction.
Indinavir (Crixivan)
Vitamin C can modestly reduce indinavir levels.
One pharmacokinetic study shows that taking vitamin C 1 gram orally once daily along with indinavir 800 mg orally three times daily reduces the area under the concentration-time curve of indinavir by 14%. The mechanism of this interaction is unknown, but it is unlikely to be clinically significant in most patients. The effect of higher doses of vitamin C on indinavir levels is unknown.
Levothyroxine (Synthroid, Others)
Vitamin C can increase levothyroxine absorption.
Two clinical studies in adults with poorly controlled hypothyroidism show that swallowing levothyroxine with a glass of water containing vitamin C 500-1000 mg in solution reduces thyroid stimulating hormone (TSH) levels and increases thyroxine (T4) levels when compared with taking levothyroxine alone. This suggests that vitamin C increases the oral absorption of levothyroxine, possibly due to a reduction in pH.
Warfarin (Coumadin)
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Vitamin C in high doses may cause diarrhea and possibly reduce warfarin absorption. There are reports of two people who took up to 16 grams daily of vitamin C and had a reduction in prothrombin time. Lower doses of 5-10 grams daily can also reduce warfarin absorption. In many cases, this does not seem to be clinically significant. However, a case of warfarin resistance has been reported for a patient who took vitamin C 500 mg twice daily. Cessation of vitamin C supplementation resulted in a rapid increase in international normalized ratio (INR). Tell patients taking warfarin to avoid taking vitamin C in excessively high doses (greater than 10 grams daily). Lower doses may be safe, but the anticoagulation activity of warfarin should be monitored. Patients who are stabilized on warfarin while taking vitamin C should avoid adjusting vitamin C dosage to prevent the possibility of warfarin resistance.
Acetaminophen (Tylenol, Others)
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
A small pharmacokinetic study in healthy volunteers shows that taking high-dose vitamin C (3 grams) 1.5 hours after taking acetaminophen 1 gram slightly increases the apparent half-life of acetaminophen from around 2.3 hours to 3.1 hours. Ascorbic acid competitively inhibits sulfate conjugation of acetaminophen. However, to compensate, elimination of acetaminophen glucuronide and unconjugated acetaminophen increases. This effect is not likely to be clinically significant.
Aspirin
Acidification of the urine by vitamin C might increase aspirin levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction is not clinically significant.
Choline Magnesium Trisalicylate (Trilisate)
Acidification of the urine by vitamin C might increase choline magnesium trisalicylate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Niacin
Vitamin C might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as vitamin C, or to the combination. It also is not known whether it will occur in other patient populations.
Salsalate (Disalcid)
Acidification of the urine by vitamin C might increase salsalate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams/day vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Sodium
Antihypertensive Drugs
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
High intake of dietary sodium can increase systolic and diastolic blood pressure. Also, high intake of sodium may necessitate increased use of antihypertensive medications to achieve blood pressure control in some patients, such as those with chronic kidney disease.
Corticosteroids
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Mineralocorticoids and some glucocorticoids (corticosteroids) cause sodium retention. This effect is dose-related and depends on mineralocorticoid potency. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Didanosine (Videx)
Concomitant use of didanosine with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia.
Didanosine formulations contain a significant amount of sodium.
Lithium
Altering dietary intake of sodium might alter the levels and clinical effects of lithium.
High sodium intake can reduce plasma concentrations of lithium by increasing lithium excretion. Reducing sodium intake can significantly increase plasma concentrations of lithium and cause lithium toxicity in patients being treated with lithium carbonate. Stabilizing sodium intake is shown to reduce the percentage of patients with lithium level fluctuations above 0.8 mEq/L. Patients taking lithium should avoid significant alterations in their dietary intake of sodium.
Sodium Phosphates
Theoretically, concomitant use of sodium phosphate with sodium supplements might increase the risk of hypernatremia.
Use of high doses (> 45 mL in 24 hours) of sodium phosphate, such as those used for bowel cleansing before surgery, can lead to serious electrolyte disturbances, including hypernatremia. The risk of hypernatremia is highest in the elderly and people with other risk factors for electrolyte disturbances.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related complications.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium supplements or high-sodium diets, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Tolvaptan (Samsca)
Theoretically, concomitant use of tolvaptan with sodium might increase the risk of hypernatremia.
Tolvaptan is a vasopressin receptor 2 antagonist that is used to increase sodium levels in patients with hyponatremia. Patients taking tolvaptan should use caution with the use of sodium salts such as sodium chloride.
Turkey Tail Mushroom
Antidiabetes Drugs
Theoretically, taking turkey tail mushroom with antidiabetes drugs might increase the risk of hypoglycemia.
Animal research suggests that turkey tail mushroom and a polysaccharide component can have hypoglycemic effects.
Cyclophosphamide
Theoretically, the polysaccharide peptide (PSP) component of turkey tail mushroom might increase exposure to cyclophosphamide.
Some animal research shows that the PSP component of turkey tail mushroom can increase the area under the concentration-time curve (AUC) of cyclophosphamide by 44% to 50% and the half-life by 34% to 43%. This interaction could potentially increase the effects and adverse effects of cyclophosphamide. However, it is not known whether PSP affects the levels of the active metabolites of cyclophosphamide that are responsible for its clinical activity.
Tamoxifen (Nolvadex)
Theoretically, the polysaccharide peptide (PSP) component of turkey tail mushroom might interfere with the absorption of tamoxifen.
Animal research suggests that PSP increases the time to reach maximum concentration of a single dose of tamoxifen by about 9.5 hours, or 228%. When repeated doses of tamoxifen were given, the time to reach maximum concentration was increased by about 5.6 hours, or 93%. However, PSP did not affect the maximum concentration or the area under the curve of tamoxifen.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, the polysaccharide peptide (PSP) component of turkey tail mushroom might inhibit CYP2C9.
Laboratory research suggests that the PSP component of turkey tail mushroom dose-dependently inhibits CYP2C9. Theoretically, taking PSP with drugs metabolized by CYP2C9 might increase drug levels and the risk of adverse effects. However, this has not been reported in humans.
Apple Cider Vinegar, Raw
Digoxin (Lanoxin)
Theoretically, concomitant use of apple cider vinegar with digoxin might increase the risk of cardiac toxicity.
A case of hypokalemia related to chronic use of apple cider vinegar has been reported. Theoretically, overuse of apple cider vinegar could decrease potassium levels, increasing the risk of toxicity with digoxin.
Diuretic Drugs
Theoretically, concomitant use of apple cider vinegar with diuretic drugs might increase the risk of hypokalemia.
A case of hypokalemia related to chronic use of apple cider vinegar has been reported. There is some concern that people taking apple cider vinegar along with potassium depleting diuretics might have an increased risk for hypokalemia.
Insulin
Theoretically, concomitant use of apple cider vinegar with insulin might increase the risk of hypokalemia.
A case of hypokalemia related to chronic use of apple cider vinegar has been reported. Theoretically, overuse of apple cider vinegar concomitantly with insulin might increase the risk of hypokalemia.
Antidiabetes Drugs
Theoretically, taking apple cider vinegar with antidiabetes drugs might increase the risk of hypoglycemia.
Apple cider vinegar might reduce fasting and postprandial blood glucose levels and decrease gastric emptying in people with diabetes. However, not all research agrees. Theoretically, it might have additive effects on glucose levels when used with antidiabetes drugs.
Brand information
Manufacturer and brand details for Alive Cola, from the product label.
Alive Cola by GT’s Alive: Common Questions
Does Alive Cola by GT’s Alive interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take this if I'm on birth control pills?
Will this help with energy?
Is this safe to take while pregnant?
What are the mushrooms in here for?
Does apple cider vinegar in this help with blood sugar?
Can I take this with warfarin (blood thinner)?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Alive Cola is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Alive Cola’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Sodium
Interacts with 205 drugsSodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets get more than enough—often too much—from...
Read the full Sodium monograph → Herb & supplement monographVitamin C
Interacts with 207 drugsVitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for immune function, collagen, and acts as an...
Read the full Vitamin C monograph → Herb & supplement monographBlack Psyllium
Interacts with 2,025 drugsBlack psyllium is a soluble-fiber supplement made from the seeds of a Plantago plant, used mostly to ease constipation and support digestive health. It is best known and most studied for rel...
Read the full Black Psyllium monograph → Herb & supplement monographReishi Mushroom
Interacts with 375 drugsReishi is a traditional Asian mushroom widely used to support the immune system and overall wellness. Human evidence for most of its claimed benefits is limited or low-quality, so it should...
Read the full Reishi Mushroom monograph → Herb & supplement monographCaffeine
Interacts with 655 drugsCaffeine is a natural stimulant found in coffee, tea, and many other plants and products. In moderate amounts it can boost alertness and reduce tiredness for most healthy adults, but too muc...
Read the full Caffeine monograph → Herb & supplement monographChaga
Interacts with 327 drugsChaga is a fungus that grows mostly on birch trees and is used as a tea or supplement, mainly for immune and antioxidant support. Human evidence for its benefits is very limited, and it may...
Read the full Chaga monograph → Herb & supplement monographApple Cider Vinegar
Interacts with 162 drugsApple cider vinegar is a fermented apple product that many people use hoping to help with blood sugar, weight, or digestion. The evidence for most of these uses is limited and mixed, and the...
Read the full Apple Cider Vinegar monograph → Herb & supplement monographTurkey Tail Mushroom
Interacts with 187 drugsTurkey tail is a woodland mushroom rich in polysaccharides like beta-glucans, and it is mainly used to support the immune system. Some of its purified extracts (PSK and PSP) have been studie...
Read the full Turkey Tail Mushroom monograph →Sources & How We Checked
Alive Cola's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 395 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Sodium 38 references
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Food and Drug Administration Science Background: Safety of Sodium Phosphates Oral Solution. September 17, 2001. Available at: http://www.fda.gov/cder/drug/safety/sodiumphospate.htm
- Coton T, Mallaret C, Coilliot C, Carre D, Guisset M. Severe acute ulcerated gastritis induced by salt. Presse Med 2009;38(3):499-500. PubMed
- Frings-Meuthen P, Buehlmeier J, Baecker N, et al. High sodium chloride intake exacerbates immobilization-induced bone resorption and protein losses. J Appl Physiol 2011;111(2):537-542. PubMed
- Frings-Meuthen P, Baecker N, Heer M. Low-grade metabolic acidosis may be the cause of sodium chloride-induced exaggerated bone resorption. J Bone Miner Res 2008;23(4):517-524. PubMed
- Alam S, Johnson AG. A meta-analysis of randomised controlled trials (RCT) among healthy normotensive and essential hypertensive elderly patients to determine the effect of high salt (NaCl) diet of blood pressure. J Hum Hypertens 1999;13(6):367-74.
- Boudville N, Ward S, Benaroia M, House AA. Increased sodium intake correlates with greater use of antihypertensive agents by subjects with chronic kidney disease. Am J Hypertens 2005;18(10):1300-5. PubMed
- Bennett WM. Drug interactions and consequences of sodium restriction. Am J Clin Nutr 1997;65(2 Suppl):678S-681S. PubMed
- Okusa MD, Crystal LJ. Clinical manifestations and management of acute lithium intoxication. Am J Med 1994;97(4):383-9. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary reference intakes for water, potassium, sodium, chloride, and sulfate. Washington, DC: National Academy Press, 2005. Available at: http://www.nap.edu/openbook.php?record_id=10925. DOI
- D'Elia L, Rossi G, Ippolito R, Cappuccio FP, Strazzullo P. Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clin Nutr 2012;31(4):489-98. PubMed
- Goldsmith SR. Hyponatremia in heart failure: time for a trial. J Card Fail 2013;19(6):398-400. PubMed
- Willocks L, Brettle R, Keen J, Valentine C, Pinching AJ. Formulations of didanosine (ddI) and salt overload. Lancet 1992;339(8786):190.
- Chen L, Zhang Z, Chen W, Whelton PK, Appel LJ. Lower Sodium Intake and Risk of Headaches: Results From the Trial of Nonpharmacologic Interventions in the Elderly. Am J Public Health. 2016;106(7):1270-5. PubMed
- Cook NR, Appel LJ, Whelton PK. Lower levels of sodium intake and reduced cardiovascular risk. Circulation. 2014;129(9):981-9. PubMed
- Cook NR, Appel LJ, Whelton PK. Sodium Intake and All-Cause Mortality Over 20 Years in the Trials of Hypertension Prevention. J Am Coll Cardiol. 2016;68(15):1609-1617. PubMed
- Mente A, O'Donnell M, Rangarajan S, et al. Associations of urinary sodium excretion with cardiovascular events in individuals with and without hypertension: a pooled analysis of data from four studies. Lancet. 2016;388(10043):465-75. PubMed
- Moosavian SP, Haghighatdoost F, Surkan PJ, Azadbakht L. Salt and obesity: a systematic review and meta-analysis of observational studies. Int J Food Sci Nutr. 2017;68(3):265-277. PubMed
- O'Donnell M, Mente A, Rangarajan S, et al. Urinary sodium and potassium excretion, mortality, and cardiovascular events. N Engl J Med. 2014;371(7):612-23. DOI
- Poggio R, Gutierrez L, Matta MG, Elorriaga N, Irazola V, Rubinstein A. Daily sodium consumption and CVD mortality in the general population: systematic review and meta-analysis of prospective studies. Public Health Nutr. 2015;18(4):695-704. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Mahtani KR, Heneghan C, Onakpoya I, et al. Reduced Salt Intake for Heart Failure: A Systematic Review. JAMA Intern Med. 2018 Dec 1;178(12):1693-1700. PubMed
- Yancy CW. Sodium Restriction in Heart Failure: Too Much Uncertainty-Do the Trials. JAMA Intern Med. 2018 Dec 1;178(12):1700-1701. PubMed
- He FJ, Campbell NRC, Ma Y, MacGregor GA, Cogswell ME, Cook NR. Errors in estimating usual sodium intake by the Kawasaki formula alter its relationship with mortality: implications for public health. Int J Epidemiol. 2018;47(6):1784-1795. PubMed
- Murthy K, Ondrey GJ, Malkani N, et al. THE EFFECTS OF HYPONATREMIA ON BONE DENSITY AND FRACTURES: A SYSTEMATIC REVIEW AND META-ANALYSIS. Endocr Pract. 2019;25(4):366-378. PubMed
- Messerli FH, Hofstetter L, Syrogiannouli L, et al. Sodium intake, life expectancy, and all-cause mortality. Eur Heart J 2021;42(21):2103-2112. PubMed
- Graudal NA, Hubeck-Graudal T, Jurgens G. Effects of low sodium diet versus high sodium diet on blood pressure, renin, aldosterone, catecholamines, cholesterol, and triglyceride. Cochrane Database Syst Rev 2020;12(12):CD004022. PubMed
- Giatti S, Santos RB, Aielo AN, et al. Association of sodium with obstructive sleep apnea. The ELSA-Brasil study. Ann Am Thorac Soc 2021;18(3):502-510. PubMed
- Nan X, Lu H, Wu J, et al. The interactive association between sodium intake, alcohol consumption and hypertension among elderly in northern China: a cross-sectional study. BMC Geriatr 2021;21(1):135. PubMed
- Kyozuka H, Fukusda T, Murata T, et al. Impact of preconception sodium intake on hypertensive disorders of pregnancy: The Japan Environment and Children's study. Pregnancy Hypertens 2021;23:66-72. PubMed
- Zhao L, Ogden CL, Yang Q, et al. Association of usual sodium intake with obesity among US children and adolescents, NHANES 2009-2016. Obesity (Silver Spring) 2021;29(3):587-594. PubMed
- Ma Y, He FJ, Sun Q, et al. 24-Hour urinary sodium and potassium excretion and cardiovascular risk. N Engl J Med 2022;386(3):252-263. PubMed
- Liu J, Yang X, Zhang P, et al. Association of urinary sodium excretion and left ventricular hypertrophy in people with type 2 diabetes mellitus: A cross-sectional study. Front Endocrinol (Lausanne) 2021;12:728493. PubMed
- Filippini T, Malavolti M, Whelton PK, Vinceti M. Sodium intake and risk of hypertension: A systematic review and dose-response meta-analysis of observational cohort studies. Curr Hypertens Rep 2022;24(5):133-144. PubMed
- Wang DD, Li Y, Nguyen XT, et al. Dietary sodium and potassium intake and risk of non-fatal cardiovascular diseases: The million veteran program. Nutrients 2022;14(5):1121. PubMed
- Kwak JH, Park CH, Eun CS, et al. The associations of dietary intake of high sodium and low zinc with gastric cancer mortality: A prospective cohort study in Korea. Nutr Cancer 2022;74(10):3501-3508. PubMed
- George S, Maiti R, Mishra BR, Jena M, Mohapatra D. Effect of regulated add-on sodium chloride intake on stabilization of serum lithium concentration in bipolar disorder: A randomized controlled trial. Bipolar Disord 2023;25(1):66-75. PubMed
- Zhou TL, Schütten MTJ, Kroon AA, et al. Urinary Sodium Excretion and Salt Intake Are Not Associated With Blood Pressure Variability in a White General Population. J Am Heart Assoc 2023;12(1):e026578. PubMed
Vitamin C 51 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Back DJ, Breckenridge AM, MacIver M, et al. Interaction of ethinyloestradiol with ascorbic acid in man. Br Med J (Clin Res Ed) 1981;282:1516.
- Morris JC, Beeley L, Ballantine N. Interaction of ethinyloestradiol with ascorbic acid in man [letter]. Br Med J (Clin Res Ed) 1981;283:503.
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Dwyer JH, Merz NB, Shirocre AM, et al. Progression of early atherosclerosis and intake of vitamin C and vitamin E from supplements and food. The Los Angeles Atherosclerosis Study. 41st Annual Conference on Cardiovascular Disease Epidemiology and Prevent
- Levine M, Rumsey SC, Daruwala R, et al. Criteria and recommendations for vitamin C intake. JAMA 1999;281:1415-23. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Houston JB, Levy G. Drug biotransformation interactions in man VI: Acetaminophen and ascorbic acid. J Pharm Sci 1976;65:1218-21. PubMed
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Rosenthal G. Interaction of ascorbic acid and warfarin. JAMA 1971;215:1671. DOI
- Hume R, Johnstone JM, Weyers E. Interaction of ascorbic acid and warfarin. JAMA 1972;219:1479. DOI
- Smith EC, Skalski RJ, Johnson GC, Rossi GV. Interaction of ascorbic acid and warfarin. JAMA 1972;221:1166. DOI
- Traxer O, Huet B, Poindexter J, et al. Effect of ascorbic acid consumption on urinary stone risk factors. J Urol 2003;170:397-401.. PubMed
- Domingo JL, Gomez M, Llobet JM, Richart C. Effect of ascorbic acid on gastrointestinal aluminum absorption (letter). Lancet 1991;338:1467.
- Domingo JL, Gomez M, Llobet JM, Corbella J. Influence of some dietary constituents on aluminum absorption and retention in rats. Kidney Int 1991;39:598-601. PubMed
- Partridge NA, Regnier FE, White JL, Hem SL. Influence of dietary constituents on intestinal absorption of aluminum. Kidney Int 1989;35:1413-7. PubMed
- Mc Leod DC, Nahata MC. Inefficacy of ascorbic acid as a urinary acidifier (letter). N Engl J Med 1977;296:1413. DOI
- Hansten PD, Hayton WL. Effect of antacid and ascorbic acid on serum salicylate concentration. J Clin Pharmacol 1980;20:326-31. PubMed
- Dysken MW, Cumming RJ, Channon RA, Davis JM. Drug interaction between ascorbic acid and fluphenazine. JAMA 1979;241:2008. DOI
- Vihtamaki T, Parantainen J, Koivisto AM, et al. Oral ascorbic acid increases plasma oestradiol during postmenopausal hormone replacement therapy. Maturitas 2002;42:129-35. PubMed
- Slain D, Amsden JR, Khakoo RA, et al. Effect of high-dose vitamin C on the steady-state pharmacokinetics of the protease inhibitor indinavir in healthy volunteers. Pharmacotherapy 2005;25:165-70. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Feetam CL, Leach RH, Meynell MJ. Lack of a clinically important interaction between warfarin and ascorbic acid. Toxicol Appl Pharmacol 1975;31:544-7. PubMed
- Weintraub M, Griner PF. Warfarin and ascorbic acid: lack of evidence for a drug interaction. Toxicol Appl Pharmacol 1974;28:53-6. PubMed
- Lee DH, Folsom AR, Harnack L, et al. Does supplemental vitamin C increase cardiovascular disease risk in women with diabetes? Am J Clin Nutr 2004;80:1194-200. PubMed
- Taylor EN, Stampfer MJ, Curhan GC. Dietary factors and the risk of incident kidney stones in men: new insights after 14 years of follow-up. J Am Soc Nephrol 2004;15:3225-32. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Fairweather-Tait S, Hickson K, McGaw B, et al. Orange juice enhances aluminium absorption from antacid preparation. Eur J Clin Nutr. 1994;48(1):71-3.
- Gruenwald, J., Graubaum, H. J., Busch, R., and Bentley, C. Safety and tolerance of ester-C compared with regular ascorbic acid. Adv.Ther. 2006;23(1):171-178.
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Einerson, B., Nathorn, C., Kitiyakara, C., Sirada, M., and Thamlikitkul, V. The efficacy of ascorbic acid in suboptimal responsive anemic hemodialysis patients receiving erythropoietin: a meta-analysis. J Med.Assoc.Thai. 2011;94 Suppl 1:S134-S146.
- Li, G., Li, L., Yu, C., and Chen, L. Effect of vitamins C and E supplementation on Helicobacter pylori eradication: a meta-analysis. Br.J Nutr 2011;106(11):1632-1637.
- Chen X, Shen L, Gu X, et al. High-dose supplementation with vitamin C--induced pediatric urolithiasis: the first case report in a child and literature review. Urology. 2014;84(4):922-4. PubMed
- Sattar A, Willman JE, Kolluri R. Possible warfarin resistance due to interaction with ascorbic acid: case report and literature review. Am J Health Syst Pharm. 2013;70(9):782-6. PubMed
- Yaich S, Chaabouni Y, Charfeddine K, et al. Secondary oxalosis due to excess vitamin C intake: a cause of graft loss in a renal transplant recipient. Saudi J Kidney Dis Transpl. 2014;25(1):113-6. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Rumbold A, Ota E, Nagata C, Shahrook S, Crowther CA. Vitamin C supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004072. PubMed
- Seo MS, Kim JK, Shim JY. High-dose vitamin C promotes regression of multiple pulmonary metastases originating from hepatocellular carcinoma. Yonsei Med J. 2015;56(5):1449-52. PubMed
- Skelin M, Lucijanic T, Amidzic Klaric D, et al. Factors Affecting Gastrointestinal Absorption of Levothyroxine: A Review. Clin Ther. 2017 Feb;39(2):378-403. PubMed
- Jiang K, Tang K, Liu H, Xu H, Ye Z, Chen Z. Ascorbic acid supplements and kidney stones incidence among men and women: a systematic review and meta-analysis. Urol J. 2019;16(2):115-120.
- Thomas S, Patel D, Bittel B, et al. Effect of High-Dose Zinc and Ascorbic Acid Supplementation vs Usual Care on Symptom Length and Reduction Among Ambulatory Patients With SARS-CoV-2 Infection: The COVID A to Z Randomized Clinical Trial. JAMA Netw Open. 2 PubMed
- Giffen MA, McLemore JL. Hyperoxalosis Secondary to Intravenous Vitamin C Administration as a Non-Allopathic Treatment for Cancer. Acad Forensic Pathol 2019;9(1-2):118-126. PubMed
- Maike A, Sturgill D, Gallan A. Oxalate Nephropathy in a Renal Transplant Recipient After Receiving High Dose Ascorbic Acid. Am J Med Sci 2021. PubMed
- Shen ZY, Chen YR, Wang MC, Chang SS. High-dose vitamin C-induced acute oxalate nephropathy in a renal transplant recipient: a case report and literature review. Asian J Surg 2022. PubMed
- Yanase F, Spano S, Maeda A, et al. Mega-dose sodium ascorbate: a pilot, single-dose, physiological effect, double-blind, randomized, controlled trial. Crit Care 2023;27(1):371. PubMed
- Sharma Y, Sumanadasa S, Shahi R, et al. Efficacy and safety of vitamin C supplementation in the treatment of community-acquired pneumonia: a systematic review and meta-analysis with trial sequential analysis. Sci Rep 2024;14(1):11846. PubMed
- Pejcic AV, Petrovic NZ, Djordjic MD, Milosavljevic MN. Vitamin C Levels in Pregnant Women and the Efficacy of Vitamin C Supplements in Preventing Premature Rupture of Membranes: A Systematic Review and Meta-Analysis. Balkan Med J 2024;41(4):248-260. PubMed
Black Psyllium 18 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Etman M. Effect of a bulk forming laxative on the bioavailablility of carbamazepine in man. Drug Dev Ind Pharm 1995;21:1901-6.
- Perlman BB. Interaction between lithium salts and ispaghula husk. Lancet 1990;335:416.
- Vaswani SK, Hamilton RG, Valentine MD, Adkinson NF. Psyllium laxative-induced anaphylaxis, asthma, and rhinitis. Allergy 1996;51:266-8. PubMed
- Lantner RR, Espiritu BR, Zumerchik P, Tobin MC. Anaphylaxis following ingestion of a psyllium-containing cereal. JAMA 1990;264:2534-6. DOI
- Kaplan MJ. Anaphylactic reaction to "Heartwise." N Engl J Med 1990;323:1072-3. DOI
- Nordstrom M, Melander A, Robertsson E, Steen B. Influence of wheat bran and of a bulk-forming ispaghula cathartic on the bioavailability of digoxin in geriatric in-patients. Drug Nutr Interact 1987;5:67-9..
- Robinson DS, Benjamin DM, McCormack JJ. Interaction of warfarin and nonsystemic gastrointestinal drugs. Clin Pharmacol Ther 1971;12:491-5. PubMed
- Garcia JJ, Fernandez N, Diez MJ, et al. Influence of two dietary fibers in the oral bioavailability and other pharmacokinetic parameters of ethinyloestradiol. Contraception 2000;62:253-7. PubMed
- Fernandez N, Lopez C, Díez R, et al. Drug interactions with the dietary fiber Plantago ovata husk. Expert Opin Drug Metab Toxicol 2012;8(11):1377-86.
- Semen plantaginis in: WHO Monographs on Selected Medicinal Plants, volume 1. World Health Organization, Geneva, 1999. Available at http://apps.who.int/medicinedocs/en/d/Js2200e/. Accessed November 26, 1026.
- Code of Federal Regulations, Title 21 (21CFR 101.17). Food labeling warning, notice, and safe handling statements. Available at www.ecfr.gov/cgi-bin/text-idx?SID=20f647d3b74161501f46564b915b4048&mc=true&node=se21.2.101_117&rgn=div8. Accessed December 3, 2
- Code of Federal Regulations, Title 21 (21CFR 201.319). Specific labeling requirements - water-soluble gums, hydrophilic gums, and hydrophilic mucilloids. Available at www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfcfr/CFRSearch.cfm?fr=201.319. Accessed Dece
- Diez R, Garcia JJ, Diez MJ, Sierra M, Sahagun AM, Fernandez N. Influence of Plantago ovata husk (dietary fiber) on the bioavailability and other pharmacokinetic parameters of metformin in diabetic rabbits. BMC Complement Altern Med. 2017 Jun 7;17(1):298. PubMed
- Chiu AC, Sherman SI. Effects of pharmacological fiber supplements on levothyroxine absorption. Thyroid. 1998;8(8):667-71. PubMed
- Merrick C, Madden CA, Capurso NA. A Case of Blunted Orally Disintegrating Olanzapine Effect Due to Coadministered Psyllium. J Clin Psychiatry 2021;82(2):20cr13633. PubMed
Reishi Mushroom 17 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Tao J, Feng KY. Experimental and clinical studies on inhibitory effect of ganoderma lucidum on platelet aggregation. J Tongji Med Univ 1990;10:240-3. PubMed
- Singh AB, Gupta SK, Pereira BM, Prakash D. Sensitization to Ganoderma lucidum in patients with respiratory allergy in India. Clin Exp Allergy 1995;25:440-7.
- Lee SY, Rhee HM. Cardiovascular effects of mycelium extract of Ganoderma lucidum: inhibition of sympathetic outflow as a mechanism of its hypotensive action. Chem Pharm Bull (Tokyo) 1990;38:1359-64. PubMed
- Kwok Y, Ng KFJ, Li, CCF, et al. A prospective, randomized, double-blind, placebo-controlled study of the platelet and global hemostatic effects of Ganoderma lucidum (Ling-Zhi) in healthy volunteers. Anesth Analg 2005;101:423-6. PubMed
- Wanmuang, H., Leopairut, J., Kositchaiwat, C., Wananukul, W., and Bunyaratvej, S. Fatal fulminant hepatitis associated with Ganoderma lucidum (Lingzhi) mushroom powder. J Med Assoc Thai. 2007;90(1):179-181.
- Seto, S. W., Lam, T. Y., Tam, H. L., Au, A. L., Chan, S. W., Wu, J. H., Yu, P. H., Leung, G. P., Ngai, S. M., Yeung, J. H., Leung, P. S., Lee, S. M., and Kwan, Y. W. Novel hypoglycemic effects of Ganoderma lucidum water-extract in obese/diabetic (+db/+db
- Chu, T. T., Benzie, I. F., Lam, C. W., Fok, B. S., Lee, K. K., and Tomlinson, B. Study of potential cardioprotective effects of Ganoderma lucidum (Lingzhi): results of a controlled human intervention trial. Br.J.Nutr. 2012;107(7):1017-1027.
- Jin, X., Ruiz, Beguerie J., Sze, D. M., and Chan, G. C. Ganoderma lucidum (Reishi mushroom) for cancer treatment. Cochrane.Database.Syst.Rev. 2012;6:CD007731.
- Kabir, Y., Kimura, S., and Tamura, T. Dietary effect of Ganoderma lucidum mushroom on blood pressure and lipid levels in spontaneously hypertensive rats (SHR). J Nutr Sci Vitaminol.(Tokyo) 1988;34(4):433-438. PubMed
- Kanmatsuse, K., Kajiwara, N., Hayashi, K., Shimogaichi, S., Fukinbara, I., Ishikawa, H., and Tamura, T. [Studies on Ganoderma lucidum. I. Efficacy against hypertension and side effects]. Yakugaku Zasshi 1985;105(10):942-947. PubMed
- Gao, Y., Lan, J., Dai, X., Ye, J., and Zhou, S. A Phase I/II Study of Ling Zhi Mushroom Ganoderma lucidum(W.Curt: Fr.) Lloyd (Aphyllophoromycetideae) Extract in Patients with Type II Diabetes Mellitus. International Journal of Medicinal Mushrooms 2004;6. DOI
- Jin H, Zhang G, Cao X, and et al. Treatment of hypertension by linzhi combined with hypotensor and its effects on arterial, arteriolar and capillary pressure and microcirculation. In: Niimi H, Xiu RJ, Sawada T, and et al. Microcirculatory Approach to Asi
- Klupp NL, Chang D, Hawke F, Kiat H, Cao H, Grant SJ, Bensoussan A. Ganoderma lucidum mushroom for the treatment of cardiovascular risk factors. Cochrane Database Syst Rev. 2015 Feb 17;2:CD007259. PubMed
- Zhao H, Zhang Q, Zhao L, Huang X, Wang J, Kang X. Spore Powder of Ganoderma lucidum Improves Cancer-Related Fatigue in Breast Cancer Patients Undergoing Endocrine Therapy: A Pilot Clinical Trial. Evid Based Complement Alternat Med. 2012;2012:809614.
- Pazzi F, Adsuar JC, Domínguez-Muñoz FJ, García-Gordillo MA, Gusi N, Collado-Mateo D. Ganoderma lucidum effects on mood and health-related quality of life in women with fibromyalgia. Healthcare (Basel) 2020;8(4):520. PubMed
- Kogure T, Koiwai A, Fukushi D, et al. Hypereosinophilia with hepatic nodule formation caused by Ganoderma lucidum. Intern Med 2021;60(24):3897-3903.
Caffeine 236 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Harder S, Fuhr U, Staib AH, Wolff T. Ciprofloxacin-caffeine: a drug interaction established using in vivo and in vitro investigations. Am J Med 1989;87:89S-91S. PubMed
- Carbo M, Segura J, De la Torre R, et al. Effect of quinolones on caffeine disposition. Clin Pharmacol Ther 1989;45:234-40. PubMed
- Healy DP, Polk RE, Kanawati L, et al. Interaction between oral ciprofloxacin and caffeine in normal volunteers. Antimicrob Agents Chemother 1989;33:474-8. PubMed
- Mester R, Toren P, Mizrachi I, et al. Caffeine withdrawal increases lithium blood levels. Biol Psychiatry 1995;37:348-50. PubMed
- Jefferson JW. Lithium tremor and caffeine intake: two cases of drinking less and shaking more. J Clin Psychiatry 1988;49:72-3.
- Joeres R, Klinker H, Heusler H, et al. Influence of mexiletine on caffeine elimination. Pharmacol Ther 1987;33:163-9. PubMed
- Vahedi K, Domingo V, Amarenco P, Bousser MG. Ischemic stroke in a sportsman who consumed MaHuang extract and creatine monohydrate for bodybuilding. J Neurol Neurosurg Psychiatr 2000;68:112-3.
- Wakabayashi K, Kono S, Shinchi K, et al. Habitual coffee consumption and blood pressure: A study of self-defense officials in Japan. Eur J Epidemiol 1998;14:669-73. PubMed
- Hodgson JM, Puddey IB, Burke V, et al. Effects on blood pressure of drinking green and black tea. J Hypertens 1999;17:457-63. PubMed
- Rapuri PB, Gallagher JC, Kinyamu HK, Ryschon KL. Caffeine intake increases the rate of bone loss in elderly women and interacts with vitamin D receptor genotypes. Am J Clin Nutr 2001;74:694-700. PubMed
- The National Toxicology Program (NTP). Caffeine. Center for the Evaluation of Risks to Human Reproduction (CERHR). Available at: http://cerhr.niehs.nih.gov/common/caffeine.html.
- Klebanoff MA, Levine RJ, DerSimonian R, et al. Maternal serum paraxanthine, a caffeine metabolite, and the risk of spontaneous abortion. N Engl J Med 1999;341:1639-44. PubMed
- Eskenazi B. Caffeine—filtering the facts. N Engl J Med 1999;341:1688-9. PubMed
- Fernandes O, Sabharwal M, Smiley T, et al. Moderate to heavy caffeine consumption during pregnancy and relationship to spontaneous abortion and abnormal fetal growth: a meta-analysis. Reprod Toxicol 1998;12:435-44. PubMed
- Pollock BG, Wylie M, Stack JA, et al. Inhibition of caffeine metabolism by estrogen replacement therapy in postmenopausal women. J Clin Pharmacol 1999;39:936-40. PubMed
- Nurminen ML, Niittynen L, Korpela R, Vapaatalo H. Coffee, caffeine and blood pressure: a critical review. Eur J Clin Nutr 1999;53:831-9. PubMed
- Dews PB, Curtis GL, Hanford KJ, O'Brien CP. The frequency of caffeine withdrawal in a population-based survey and in a controlled, blinded pilot experiment. J Clin Pharmacol 1999;39:1221-32. PubMed
- FDA. Proposed rule: dietary supplements containing ephedrine alkaloids. Available at: www.verity.fda.gov (Accessed 25 January 2000).
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Hagg S, Spigset O, Mjorndal T, Dahlqvist R. Effect of caffeine on clozapine pharmacokinetics in healthy volunteers. Br J Clin Pharmacol 2000;49:59-63. PubMed
- Tobias JD. Caffeine in the treatment of apnea associated with respiratory syncytial virus infection in neonates and infants. South Med J 2000;93:297-304. DOI
- Watson JM, Jenkins EJ, Hamilton P, et al. Influence of caffeine on the frequency and perception of hypoglycemia in free-living patients with type 1 diabetes. Diabetes Care 2000;23:455-9. PubMed
- Lloyd T, Johnson-Rollings N, Eggli DF, et al. Bone status among postmenopausal women with different habitual caffeine intakes: a longitudinal investigation. J Am Coll Nutr 2000;19:256-61. PubMed
- American Academy of Pediatrics. The transfer of drugs and other chemicals into human milk. Pediatrics 2001;108:776-89. PubMed
- Sinclair CJ, Geiger JD. Caffeine use in sports. A pharmacological review. J Sports Med Phys Fitness 2000;40:71-9.
- Haller CA, Benowitz NL. Adverse cardiovascular and central nervous system events associated with dietary supplements containing ephedra alkaloids. N Engl J Med 2000;343:1833-8. PubMed
- Ali M, Afzal M. A potent inhibitor of thrombin stimulated platelet thromboxane formation from unprocessed tea. Prostaglandins Leukot Med 1987;27:9-13. PubMed
- Ardlie NG, Glew G, Schultz BG, Schwartz CJ. Inhibition and reversal of platelet aggregation by methyl xanthines. Thromb Diath Haemorrh 1967;18:670-3. DOI
- Ferrini RL, Barrett-Connor E. Caffeine intake and endogenous sex steroid levels in postmenopausal women. The Rancho Bernardo Study. Am J Epidemiol 1996:144:642-4. PubMed
- Avisar R, Avisar E, Weinberger D. Effect of coffee consumption on intraocular pressure. Ann Pharmacother 2002;36:992-5.. PubMed
- Bell DG, Jacobs I, Ellerington K. Effect of caffeine and ephedrine ingestion on anaerobic exercise performance. Med Sci Sports Exerc 2001;33:1399-403. PubMed
- Horner NK, Lampe JW. Potential mechanisms of diet therapy for fibrocystic breast conditions show inadequate evidence of effectiveness. J Am Diet Assoc 2000;100:1368-80. PubMed
- Bracken MB, Triche EW, Belanger K, et al. Association of maternal caffeine consumption with decrements in fetal growth. Am J Epidemiol 2003;157:456-66.. PubMed
- McGowan JD, Altman RE, Kanto WP Jr. Neonatal withdrawal symptoms after chronic maternal ingestion of caffeine. South Med J 1988;81:1092-4.. PubMed
- Massey LK. Is caffeine a risk factor for bone loss in the elderly? Am J Clin Nutr 2001;74:569-70. PubMed
- Dreher HM. The effect of caffeine reduction on sleep quality and well-being in persons with HIV. J Psychosom Res 2003;54:191-8.. PubMed
- Kockler DR, McCarthy MW, Lawson CL. Seizure activity and unresponsiveness after hydroxycut ingestion. Pharmacotherapy 2001;21:647-51.. PubMed
- Schechter MD, Timmons GD. Objectively measured hyperactivity--II. Caffeine and amphetamine effects. J Clin Pharmacol 1985;25:276-80.. PubMed
- Nix D, Zelenitsky S, Symonds W, et al. The effect of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. Clin Pharmacol Ther 1992;51:183. DOI
- Infante S, Baeza ML, Calvo M, et al. Anaphylaxis due to caffeine. Allergy 2003;58:681-2. PubMed
- Massey LK, Whiting SJ. Caffeine, urinary calcium, calcium metabolism and bone. J Nutr 1993;123:1611-4. PubMed
- Nawrot P, Jordan S, Eastwood J, et al. Effects of caffeine on human health. Food Addit Contam 2003;20:1-30. PubMed
- May DC, Jarboe CH, VanBakel AB, Williams WM. Effects of cimetidine on caffeine disposition in smokers and nonsmokers. Clin Pharmacol Ther 1982;31:656-61. PubMed
- Abernethy DR, Todd EL. Impairment of caffeine clearance by chronic use of low-dose oestrogen-containing oral contraceptives. Eur J Clin Pharmacol 1985;28:425-8. PubMed
- Brown NJ, Ryder D, Branch RA. A pharmacodynamic interaction between caffeine and phenylpropanolamine. Clin Pharmacol Ther 1991;50:363-71. PubMed
- Sanderink GJ, Bournique B, Stevens J, et al. Involvement of human CYP1A isoenzymes in the metabolism and drug interactions of riluzole in vitro. Pharmacol Exp Ther 1997;282:1465-72. DOI
- Wahllander A, Paumgartner G. Effect of ketoconazole and terbinafine on the pharmacokinetics of caffeine in healthy volunteers. Eur J Clin Pharmacol 1989;37:279-83. PubMed
- Carrillo JA, Benitez J. Clinically significant pharmacokinetic interactions between dietary caffeine and medications. Clin Pharmacokinet 2000;39:127-53. PubMed
- Underwood DA. Which medications should be held before a pharmacologic or exercise stress test? Cleve Clin J Med 2002;69:449-50. PubMed
- Aqel RA, Zoghbi GJ, Trimm JR, et al. Effect of caffeine administered intravenously on intracoronary-administered adenosine-induced coronary hemodynamics in patients with coronary artery disease. Am J Cardiol 2004;93:343-6. PubMed
- Zheng XM, Williams RC. Serum caffeine levels after 24-hour abstention: clinical implications on dipyridamole (201)Tl myocardial perfusion imaging. J Nucl Med Technol 2002;30:123-7.
- Institute of Medicine. Caffeine for the Sustainment of Mental Task Performance: Formulations for Military Operations. Washington, DC: National Academy Press, 2001. Available at: http://books.nap.edu/books/0309082587/html/index.html. DOI
- Dews PB, O'Brien CP, Bergman J. Caffeine: behavioral effects of withdrawal and related issues. Food Chem Toxicol 2002;40:1257-61. PubMed
- Beach CA, Mays DC, Guiler RC, et al. Inhibition of elimination of caffeine by disulfiram in normal subjects and recovering alcoholics. Clin Pharmacol Ther 1986;39:265-70. PubMed
- Juliano LM, Griffiths RR. A critical review of caffeine withdrawal: empirical validation of symptoms and signs, incidence, severity, and associated features. Psychopharmacology (Berl) 2004;176:1-29. PubMed
- Winkelmayer WC, Stampfer MJ, Willett WC, Curhan GC. Habitual caffeine intake and the risk of hypertension in women. JAMA 2005;294:2330-5. PubMed
- Raaska K, Raitasuo V, Laitila J, Neuvonen PJ. Effect of caffeine-containing versus decaffeinated coffee on serum clozapine concentrations in hospitalised patients. Basic Clin Pharmacol Toxicol 2004;94:13-8. DOI
- Forrest WH Jr, Bellville JW, Brown BW Jr. The interaction of caffeine with pentobarbital as a nighttime hypnotic. Anesthesiology 1972;36:37-41. PubMed
- Lake CR, Rosenberg DB, Gallant S, et al. Phenylpropanolamine increases plasma caffeine levels. Clin Pharmacol Ther 1990;47:675-85. PubMed
- Weng X, Odouli R, Li DK. Maternal caffeine consumption during pregnancy and the risk of miscarriage: a prospective cohort study. Am J Obstet Gynecol 2008;198:279.e1-8. PubMed
- Savitz DA, Chan RL, Herring AH, et al. Caffeine and miscarriage risk. Epidemiology 2008;19:55-62. PubMed
- Shet, M. S., McPhaul, M., Fisher, C. W., Stallings, N. R., and Estabrook, R. W. Metabolism of the antiandrogenic drug (Flutamide) by human CYP1A2. Drug Metab Dispos. 1997;25(11):1298-1303.
- Staib, A. H., Stille, W., Dietlein, G., Shah, P. M., Harder, S., Mieke, S., and Beer, C. Interaction between quinolones and caffeine. Drugs 1987;34 Suppl 1:170-174. PubMed
- Stille, W., Harder, S., Mieke, S., Beer, C., Shah, P. M., Frech, K., and Staib, A. H. Decrease of caffeine elimination in man during co-administration of 4-quinolones. J.Antimicrob.Chemother. 1987;20(5):729-734. PubMed
- Fuhr, U., Strobl, G., Manaut, F., Anders, E. M., Sorgel, F., Lopez-de-Brinas, E., Chu, D. T., Pernet, A. G., Mahr, G., Sanz, F., and . Quinolone antibacterial agents: relationship between structure and in vitro inhibition of the human cytochrome P450 isof
- Kot, M. and Daniel, W. A. Effect of diethyldithiocarbamate (DDC) and ticlopidine on CYP1A2 activity and caffeine metabolism: an in vitro comparative study with human cDNA-expressed CYP1A2 and liver microsomes. Pharmacol Rep. 2009;61(6):1216-1220. PubMed
- Gasior, M., Borowicz, K., Buszewicz, G., Kleinrok, Z., and Czuczwar, S. J. Anticonvulsant activity of phenobarbital and valproate against maximal electroshock in mice during chronic treatment with caffeine and caffeine discontinuation. Epilepsia 1996;37(3 PubMed
- Jankiewicz, K., Chroscinska-Krawczyk, M., Blaszczyk, B., and Czuczwar, S. J. [Caffeine and antiepileptic drugs: experimental and clinical data]. Przegl.Lek. 2007;64(11):965-967.
- Luszczki, J. J., Zuchora, M., Sawicka, K. M., Kozinska, J., and Czuczwar, S. J. Acute exposure to caffeine decreases the anticonvulsant action of ethosuximide, but not that of clonazepam, phenobarbital and valproate against pentetrazole-induced seizures i
- Chroscinska-Krawczyk, M., Jargiello-Baszak, M., Walek, M., Tylus, B., and Czuczwar, S. J. Caffeine and the anticonvulsant potency of antiepileptic drugs: experimental and clinical data. Pharmacol.Rep. 2011;63(1):12-18. PubMed
- Vaz, J., Kulkarni, C., David, J., and Joseph, T. Influence of caffeine on pharmacokinetic profile of sodium valproate and carbamazepine in normal human volunteers. Indian J.Exp.Biol. 1998;36(1):112-114.
- Gasior, M., Swiader, M., Przybylko, M., Borowicz, K., Turski, W. A., Kleinrok, Z., and Czuczwar, S. J. Felbamate demonstrates low propensity for interaction with methylxanthines and Ca2+ channel modulators against experimental seizures in mice. Eur.J Phar PubMed
- Balogh, A., Klinger, G., Henschel, L., Borner, A., Vollanth, R., and Kuhnz, W. Influence of ethinylestradiol-containing combination oral contraceptives with gestodene or levonorgestrel on caffeine elimination. Eur.J.Clin.Pharmacol. 1995;48(2):161-166. PubMed
- Mohiuddin, M., Azam, A. T., Amran, M. S., and Hossain, M. A. In vive effects of gliclazide and metformin on the plasma concentration of caffeine in healthy rats. Pak.J Biol Sci 5-1-2009;12(9):734-737.
- Mays, D. C., Camisa, C., Cheney, P., Pacula, C. M., Nawoot, S., and Gerber, N. Methoxsalen is a potent inhibitor of the metabolism of caffeine in humans. Clin.Pharmacol.Ther. 1987;42(6):621-626. PubMed
- Wojcikowski, J. and Daniel, W. A. Perazine at therapeutic drug concentrations inhibits human cytochrome P450 isoenzyme 1A2 (CYP1A2) and caffeine metabolism--an in vitro study. Pharmacol Rep. 2009;61(5):851-858. PubMed
- Daniel, W. A., Syrek, M., Rylko, Z., and Kot, M. Effects of phenothiazine neuroleptics on the rate of caffeine demethylation and hydroxylation in the rat liver. Pol.J Pharmacol 2001;53(6):615-621.
- Norager, C. B., Jensen, M. B., Weimann, A., and Madsen, M. R. Metabolic effects of caffeine ingestion and physical work in 75-year old citizens. A randomized, double-blind, placebo-controlled, cross-over study. Clin Endocrinol (Oxf) 2006;65(2):223-228. PubMed
- Bailey, D. N., Weibert, R. T., Naylor, A. J., and Shaw, R. F. A study of salicylate and caffeine excretion in the breast milk of two nursing mothers. J.Anal.Toxicol. 1982;6(2):64-68. PubMed
- Griffiths, R. R. and Chausmer, A. L. Caffeine as a model drug of dependence: recent developments in understanding caffeine withdrawal, the caffeine dependence syndrome, and caffeine negative reinforcement. Nihon Shinkei Seishin Yakurigaku Zasshi 2000;20(
- Karacan, I., Thornby, J. I., Anch, M., Booth, G. H., Williams, R. L., and Salis, P. J. Dose-related sleep disturbances induced by coffee and caffeine. Clin Pharmacol Ther 1976;20(6):682-689. PubMed
- Quirce, G. S., Freire, P., Fernandez, R. M., Davila, I., and Losada, E. Urticaria from caffeine. J.Allergy Clin Immunol. 1991;88(4):680-681. PubMed
- Hughes, J. R., Higgins, S. T., Bickel, W. K., Hunt, W. K., Fenwick, J. W., Gulliver, S. B., and Mireault, G. C. Caffeine self-administration, withdrawal, and adverse effects among coffee drinkers. Arch.Gen.Psychiatry 1991;48(7):611-617. PubMed
- Adams, B. A. and Brubaker, R. F. Caffeine has no clinically significant effect on aqueous humor flow in the normal human eye. Ophthalmology 1990;97(8):1030-1031. PubMed
- Davis, R. H. Does caffeine ingestion affect intraocular pressure?. Ophthalmology 1989;96(11):1680-1681. PubMed
- Higginbotham, E. J., Kilimanjaro, H. A., Wilensky, J. T., Batenhorst, R. L., and Hermann, D. The effect of caffeine on intraocular pressure in glaucoma patients. Ophthalmology 1989;96(5):624-626.
- Wrenn, K. D. and Oschner, I. Rhabdomyolysis induced by a caffeine overdose. Ann.Emerg.Med. 1989;18(1):94-97. PubMed
- Pola, J., Subiza, J., Armentia, A., Zapata, C., Hinojosa, M., Losada, E., and Valdivieso, R. Urticaria caused by caffeine. Ann.Allergy 1988;60(3):207-208.
- Lane, J. D. and Williams, R. B., Jr. Cardiovascular effects of caffeine and stress in regular coffee drinkers. Psychophysiology 1987;24(2):157-164. PubMed
- Shirlow, M. J. and Mathers, C. D. A study of caffeine consumption and symptoms; indigestion, palpitations, tremor, headache and insomnia. Int.J.Epidemiol. 1985;14(2):239-248. PubMed
- Stillner, V., Popkin, M. K., and Pierce, C. M. Caffeine-induced delirium during prolonged competitive stress. Am.J.Psychiatry 1978;135(7):855-856. PubMed
- Levy, M. and Zylber-Katz, E. Caffeine metabolism and coffee-attributed sleep disturbances. Clin Pharmacol Ther 1983;33(6):770-775. PubMed
- Brown, S. L., Salive, M. E., Pahor, M., Foley, D. J., Corti, M. C., Langlois, J. A., Wallace, R. B., and Harris, T. B. Occult caffeine as a source of sleep problems in an older population. J.Am.Geriatr.Soc. 1995;43(8):860-864. PubMed
- Sung, B. H., Whitsett, T. L., Lovallo, W. R., al'Absi, M., Pincomb, G. A., and Wilson, M. F. Prolonged increase in blood pressure by a single oral dose of caffeine in mildly hypertensive men. Am.J Hypertens. 1994;7(8):755-758. PubMed
- Caballero, T., Garcia-Ara, C., Pascual, C., Diaz-Pena, J. M., and Ojeda, A. Urticaria induced by caffeine. J.Investig.Allergol.Clin Immunol. 1993;3(3):160-162.
- Smits, P., Temme, L., and Thien, T. The cardiovascular interaction between caffeine and nicotine in humans. Clin Pharmacol Ther 1993;54(2):194-204. PubMed
- Garrett, B. E. and Griffiths, R. R. Physical dependence increases the relative reinforcing effects of caffeine versus placebo. Psychopharmacology (Berl) 1998;139(3):195-202. PubMed
- Lane, J. D. and Phillips-Bute, B. G. Caffeine deprivation affects vigilance performance and mood. Physiol Behav. 1998;65(1):171-175. PubMed
- Boekema, P. J., Samsom, M., van Berge Henegouwen, G. P., and Smout, A. J. Coffee and gastrointestinal function: facts and fiction. A review. Scand J Gastroenterol.Suppl 1999;230:35-39. PubMed
- Terry, P., Lagergren, J., Wolk, A., and Nyren, O. Reflux-inducing dietary factors and risk of adenocarcinoma of the esophagus and gastric cardia. Nutr Cancer 2000;38(2):186-191.
- Pollak, C. P. and Bright, D. Caffeine consumption and weekly sleep patterns in US seventh-, eighth-, and ninth-graders. Pediatrics 2003;111(1):42-46. PubMed
- DiBaise, J. K. A randomized, double-blind comparison of two different coffee-roasting processes on development of heartburn and dyspepsia in coffee-sensitive individuals. Dig.Dis.Sci 2003;48(4):652-656. PubMed
- Wang, J. H., Luo, J. Y., Dong, L., Gong, J., and Tong, M. Epidemiology of gastroesophageal reflux disease: a general population-based study in Xi'an of Northwest China. World J Gastroenterol. 6-1-2004;10(11):1647-1651. PubMed
- Naliboff, B. D., Mayer, M., Fass, R., Fitzgerald, L. Z., Chang, L., Bolus, R., and Mayer, E. A. The effect of life stress on symptoms of heartburn. Psychosom.Med 2004;66(3):426-434. PubMed
- Massey, L. K. and Sutton, R. A. Acute caffeine effects on urine composition and calcium kidney stone risk in calcium stone formers. J.Urol. 2004;172(2):555-558. PubMed
- Tavani, A. and La, Vecchia C. Coffee, decaffeinated coffee, tea and cancer of the colon and rectum: a review of epidemiological studies, 1990-2003. Cancer Causes Control 2004;15(8):743-757. PubMed
- Noordzij, M., Uiterwaal, C. S., Arends, L. R., Kok, F. J., Grobbee, D. E., and Geleijnse, J. M. Blood pressure response to chronic intake of coffee and caffeine: a meta-analysis of randomized controlled trials. J Hypertens. 2005;23(5):921-928. PubMed
- Chandrasekaran, S., Rochtchina, E., and Mitchell, P. Effects of caffeine on intraocular pressure: the Blue Mountains Eye Study. J Glaucoma. 2005;14(6):504-507. PubMed
- Morgan, J. C. and Sethi, K. D. Drug-induced tremors. Lancet Neurol. 2005;4(12):866-876. PubMed
- Doan, B. K., Hickey, P. A., Lieberman, H. R., and Fischer, J. R. Caffeinated tube food effect on pilot performance during a 9-hour, simulated nighttime U-2 mission. Aviat.Space Environ Med 2006;77(10):1034-1040.
- Whalen, D. J., Silk, J. S., Semel, M., Forbes, E. E., Ryan, N. D., Axelson, D. A., Birmaher, B., and Dahl, R. E. Caffeine consumption, sleep, and affect in the natural environments of depressed youth and healthy controls. J Pediatr.Psychol. 2008;33(4):35 PubMed
- MacKenzie, T., Comi, R., Sluss, P., Keisari, R., Manwar, S., Kim, J., Larson, R., and Baron, J. A. Metabolic and hormonal effects of caffeine: randomized, double-blind, placebo-controlled crossover trial. Metabolism 2007;56(12):1694-1698. PubMed
- Mort, J. R. and Kruse, H. R. Timing of blood pressure measurement related to caffeine consumption. Ann Pharmacother. 2008;42(1):105-110.
- Ganmaa, D., Willett, W. C., Li, T. Y., Feskanich, D., van Dam, R. M., Lopez-Garcia, E., Hunter, D. J., and Holmes, M. D. Coffee, tea, caffeine and risk of breast cancer: a 22-year follow-up. Int J Cancer 5-1-2008;122(9):2071-2076. PubMed
- Killgore, W. D., Rupp, T. L., Grugle, N. L., Reichardt, R. M., Lipizzi, E. L., and Balkin, T. J. Effects of dextroamphetamine, caffeine and modafinil on psychomotor vigilance test performance after 44 h of continuous wakefulness. J Sleep Res 2008;17(3):3 PubMed
- Ozsungur, S., Brenner, D., and El-Sohemy, A. Fourteen well-described caffeine withdrawal symptoms factor into three clusters. Psychopharmacology (Berl) 2009;201(4):541-548. PubMed
- Ishitani, K., Lin, J., Manson, J. E., Buring, J. E., and Zhang, S. M. Caffeine consumption and the risk of breast cancer in a large prospective cohort of women. Arch Intern Med 10-13-2008;168(18):2022-2031. PubMed
- Tunnicliffe, J. M., Erdman, K. A., Reimer, R. A., Lun, V., and Shearer, J. Consumption of dietary caffeine and coffee in physically active populations: physiological interactions. Appl Physiol Nutr Metab 2008;33(6):1301-1310. PubMed
- Sin, C. W., Ho, J. S., and Chung, J. W. Systematic review on the effectiveness of caffeine abstinence on the quality of sleep. J Clin Nurs. 2009;18(1):13-21. PubMed
- Lopez-Garcia, E., Rodriguez-Artalejo, F., Rexrode, K. M., Logroscino, G., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of stroke in women. Circulation 3-3-2009;119(8):1116-1123. PubMed
- Zhang, W., Lopez-Garcia, E., Li, T. Y., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of cardiovascular diseases and all-cause mortality among men with type 2 diabetes. Diabetes Care 2009;32(6):1043-1045. PubMed
- Killgore, W. D., Kahn-Greene, E. T., Grugle, N. L., Killgore, D. B., and Balkin, T. J. Sustaining executive functions during sleep deprivation: A comparison of caffeine, dextroamphetamine, and modafinil. Sleep 2-1-2009;32(2):205-216. PubMed
- Natale, F., Cirillo, C., Di Marco, G. M., di Vetta, L. S., Aronne, L., Siciliano, A., Mocerino, R., Tedesco, M. A., Golino, P., and Calabro, R. When chewing gum is more than just a bad habit. Lancet 5-30-2009;373(9678):1918. PubMed
- Calamaro, C. J., Mason, T. B., and Ratcliffe, S. J. Adolescents living the 24/7 lifestyle: effects of caffeine and technology on sleep duration and daytime functioning. Pediatrics 2009;123(6):e1005-e1010. PubMed
- Koran, L. M., Aboujaoude, E., and Gamel, N. N. Double-blind study of dextroamphetamine versus caffeine augmentation for treatment-resistant obsessive-compulsive disorder. J Clin Psychiatry 2009;70(11):1530-1535. PubMed
- Luebbe, A. M. and Bell, D. J. Mountain Dew or mountain don't?: a pilot investigation of caffeine use parameters and relations to depression and anxiety symptoms in 5th- and 10th-grade students. J Sch Health 2009;79(8):380-387.
- Skouroliakou, M., Bacopoulou, F., and Markantonis, S. L. Caffeine versus theophylline for apnea of prematurity: a randomised controlled trial. J Paediatr.Child Health 2009;45(10):587-592. PubMed
- Urade, Y. [Molecular mechanisms of insomnia]. Nippon Rinsho 2009;67(8):1489-1493.
- Montandon, G., Horner, R. L., Kinkead, R., and Bairam, A. Caffeine in the neonatal period induces long-lasting changes in sleep and breathing in adult rats. J Physiol 11-15-2009;587(Pt 22):5493-5507. PubMed
- Addicott, M. A. and Laurienti, P. J. A comparison of the effects of caffeine following abstinence and normal caffeine use. Psychopharmacology (Berl) 2009;207(3):423-431. PubMed
- Hashim, H. and Al, Mousa R. Management of fluid intake in patients with overactive bladder. Curr.Urol.Rep. 2009;10(6):428-433. PubMed
- Moisey, L. L., Robinson, L. E., and Graham, T. E. Consumption of caffeinated coffee and a high carbohydrate meal affects postprandial metabolism of a subsequent oral glucose tolerance test in young, healthy males. Br.J Nutr. 2010;103(6):833-841. PubMed
- Chroscinska-Krawczyk, M., Ratnaraj, N., Patsalos, P. N., and Czuczwar, S. J. Effect of caffeine on the anticonvulsant effects of oxcarbazepine, lamotrigine and tiagabine in a mouse model of generalized tonic-clonic seizures. Pharmacol Rep. 2009;61(5):819 PubMed
- Attwood, A., Terry, P., and Higgs, S. Conditioned effects of caffeine on performance in humans. Physiol Behav 3-3-2010;99(3):286-293. PubMed
- Skinner, T. L., Jenkins, D. G., Coombes, J. S., Taaffe, D. R., and Leveritt, M. D. Dose response of caffeine on 2000-m rowing performance. Med Sci Sports Exerc. 2010;42(3):571-576. PubMed
- Holick, C. N., Smith, S. G., Giovannucci, E., and Michaud, D. S. Coffee, tea, caffeine intake, and risk of adult glioma in three prospective cohort studies. Cancer Epidemiol.Biomarkers Prev 2010;19(1):39-47. PubMed
- Simmonds, M. J., Minahan, C. L., and Sabapathy, S. Caffeine improves supramaximal cycling but not the rate of anaerobic energy release. Eur.J Appl Physiol 2010;109(2):287-295. PubMed
- Buscemi, S., Verga, S., Batsis, J. A., Donatelli, M., Tranchina, M. R., Belmonte, S., Mattina, A., Re, A., and Cerasola, G. Acute effects of coffee on endothelial function in healthy subjects. Eur.J Clin Nutr. 2010;64(5):483-489. PubMed
- Rigato, I., Blarasin, L., and Kette, F. Severe hypokalemia in 2 young bicycle riders due to massive caffeine intake. Clin J Sport Med. 2010;20(2):128-130. PubMed
- Greenwood, D. C., Alwan, N., Boylan, S., Cade, J. E., Charvill, J., Chipps, K. C., Cooke, M. S., Dolby, V. A., Hay, A. W., Kassam, S., Kirk, S. F., Konje, J. C., Potdar, N., Shires, S., Simpson, N., Taub, N., Thomas, J. D., Walker, J., White, K. L., and
- Mevcha, A., Gulur, D. M., and Gillatt, D. Diagnosing urological disorders in ageing men. Practitioner 2010;254(1726):25-9, 2.
- Brick, C. A., Seely, D. L., and Palermo, T. M. Association between sleep hygiene and sleep quality in medical students. Behav Sleep Med 2010;8(2):113-121. PubMed
- Digdon, N. L. Circadian preference and college students' beliefs about sleep education. Chronobiol.Int 2010;27(2):297-317. PubMed
- Boos, C. J., White, S. H., Bland, S. A., and McAllister, P. D. Dietary supplements and military operations: caution is advised. J R.Army Med Corps 2010;156(1):41-43. PubMed
- Casiglia, E., Bongiovi, S., Paleari, C. D., Petucco, S., Boni, M., Colangeli, G., Penzo, M., and Pessina, A. C. Haemodynamic effects of coffee and caffeine in normal volunteers: a placebo-controlled clinical study. J.Intern.Med. 1991;229(6):501-504. PubMed
- Aguggia, M. and Saracco, M. G. Pathophysiology of migraine chronification. Neurol.Sci 2010;31 Suppl 1:S15-S17. PubMed
- Torelli, P. and Manzoni, G. C. Fasting headache. Curr Pain Headache Rep. 2010;14(4):284-291.
- Farag, N. H., Whitsett, T. L., McKey, B. S., Wilson, M. F., Vincent, A. S., Everson-Rose, S. A., and Lovallo, W. R. Caffeine and blood pressure response: sex, age, and hormonal status. J Womens Health (Larchmt.) 2010;19(6):1171-1176. PubMed
- Ernest, D., Chia, M., and Corallo, C. E. Profound hypokalaemia due to Nurofen Plus and Red Bull misuse. Crit Care Resusc. 2010;12(2):109-110. DOI
- Suen, L. K., Tam, W. W., and Hon, K. L. Association of sleep hygiene-related factors and sleep quality among university students in Hong Kong. Hong.Kong.Med.J 2010;16(3):180-185.
- Stafford, L. D., Wright, C., and Yeomans, M. R. The drink remains the same: implicit positive associations in high but not moderate or non-caffeine users. Psychol.Addict.Behav. 2010;24(2):274-281. PubMed
- Conen, D., Chiuve, S. E., Everett, B. M., Zhang, S. M., Buring, J. E., and Albert, C. M. Caffeine consumption and incident atrial fibrillation in women. Am J Clin Nutr 2010;92(3):509-514. PubMed
- Freire, R. C., Perna, G., and Nardi, A. E. Panic disorder respiratory subtype: psychopathology, laboratory challenge tests, and response to treatment. Harv.Rev.Psychiatry 2010;18(4):220-229. PubMed
- Reis, J. P., Loria, C. M., Steffen, L. M., Zhou, X., van, Horn L., Siscovick, D. S., Jacobs, D. R., Jr., and Carr, J. J. Coffee, decaffeinated coffee, caffeine, and tea consumption in young adulthood and atherosclerosis later in life: the CARDIA study. A PubMed
- Clausen, T. Hormonal and pharmacological modification of plasma potassium homeostasis. Fundam.Clin Pharmacol 2010;24(5):595-605. PubMed
- Kujawa-Hadrys, M., Tosik, D., and Bartel, H. Changes in thickness of each layer of developing chicken cornea after administration of caffeine. Folia Histochem.Cytobiol. 2010;48(2):273-277. PubMed
- Boggs, D. A., Palmer, J. R., Stampfer, M. J., Spiegelman, D., Adams-Campbell, L. L., and Rosenberg, L. Tea and coffee intake in relation to risk of breast cancer in the Black Women's Health Study. Cancer Causes Control 2010;21(11):1941-1948. PubMed
- Li, S., Zhu, S., Jin, X., Yan, C., Wu, S., Jiang, F., and Shen, X. Risk factors associated with short sleep duration among Chinese school-aged children. Sleep Med. 2010;11(9):907-916. PubMed
- Gronroos, N. N. and Alonso, A. Diet and risk of atrial fibrillation - epidemiologic and clinical evidence -. Circ.J 2010;74(10):2029-2038. PubMed
- Knight, J. M., Avery, E. F., Janssen, I., and Powell, L. H. Cortisol and depressive symptoms in a population-based cohort of midlife women. Psychosom.Med. 2010;72(9):855-861. PubMed
- Porkka-Heiskanen, T. Methylxanthines and sleep. Handb.Exp.Pharmacol 2011;(200):331-348. PubMed
- Mostofsky, E., Schlaug, G., Mukamal, K. J., Rosamond, W. D., and Mittleman, M. A. Coffee and acute ischemic stroke onset: the Stroke Onset Study. Neurology 11-2-2010;75(18):1583-1588. PubMed
- Orozco-Gregorio, H., Mota-Rojas, D., Bonilla-Jaime, H., Trujillo-Ortega, M. E., Becerril-Herrera, M., Hernandez-Gonzalez, R., and Villanueva-Garcia, D. Effects of administration of caffeine on metabolic variables in neonatal pigs with peripartum asphyxia PubMed
- Li, G. Z., Zhang, N., Du, P., Yang, Y., Wu, S. L., Xiao, Y. X., Jin, R., Liu, L., Shen, H., and Dai, Y. Risk factors for interstitial cystitis/painful bladder syndrome in patients with lower urinary tract symptoms: a Chinese multi-center study. Chin Med
- Duvnjak-Zaknich, D. M., Dawson, B. T., Wallman, K. E., and Henry, G. Effect of caffeine on reactive agility time when fresh and fatigued. Med.Sci.Sports Exerc. 2011;43(8):1523-1530. PubMed
- Astorino, T. A., Martin, B. J., Schachtsiek, L., Wong, K., and Ng, K. Minimal effect of acute caffeine ingestion on intense resistance training performance. J Strength.Cond.Res 2011;25(6):1752-1758. PubMed
- Kivity, S., Ben Aharon, Y., Man, A., and Topilsky, M. The effect of caffeine on exercise-induced bronchoconstriction. Chest 1990;97(5):1083-1085. PubMed
- Lubin, F. and Ron, E. Consumption of methylxanthine-containing beverages and the risk of breast cancer. Cancer Lett. 1990;53(2-3):81-90. PubMed
- Smits, P., Lenders, J. W., and Thien, T. Caffeine and theophylline attenuate adenosine-induced vasodilation in humans. Clin.Pharmacol.Ther. 1990;48(4):410-418. PubMed
- Rossignol, A. M. and Bonnlander, H. Caffeine-containing beverages, total fluid consumption, and premenstrual syndrome. Am.J.Public Health 1990;80(9):1106-1110. PubMed
- Birkett, N. J. and Logan, A. G. Caffeine-containing beverages and the prevalence of hypertension. J Hypertens.Suppl 1988;6(4):S620-S622. PubMed
- Fraumeni, J. F., Jr., Scotto, J., and Dunham, L. J. Coffee-drinking and bladder cancer. Lancet 11-27-1971;2(7735):1204. PubMed
- Greden, J. F. Anxiety or caffeinism: a diagnostic dilemma. Am J Psychiatry 1974;131(10):1089-1092. PubMed
- Whitsett, T. L., Manion, C. V., and Christensen, H. D. Cardiovascular effects of coffee and caffeine. Am.J.Cardiol. 3-15-1984;53(7):918-922. PubMed
- Firestone, P., Poitras-Wright, H., and Douglas, V. The effects of caffeine on hyperactive children. J.Learn.Disabil. 1978;11(3):133-141. PubMed
- Thomas, F. B., Steinbaugh, J. T., Fromkes, J. J., Mekhjian, H. S., and Caldwell, J. H. Inhibitory effect of coffee on lower esophageal sphincter pressure. Gastroenterology 1980;79(6):1262-1266. DOI
- Linn, S., Schoenbaum, S. C., Monson, R. R., Rosner, B., Stubblefield, P. G., and Ryan, K. J. No association between coffee consumption and adverse outcomes of pregnancy. N.Engl.J Med 1-21-1982;306(3):141-145. PubMed
- Cohen, S. Pathogenesis of coffee-induced gastrointestinal symptoms. N.Engl.J Med 7-17-1980;303(3):122-124. PubMed
- Feldman, M. and Barnett, C. Relationships between the acidity and osmolality of popular beverages and reported postprandial heartburn. Gastroenterology 1995;108(1):125-131. PubMed
- Quinlan, P., Lane, J., and Aspinall, L. Effects of hot tea, coffee and water ingestion on physiological responses and mood: the role of caffeine, water and beverage type. Psychopharmacology (Berl) 1997;134(2):164-173. PubMed
- Youngstedt, S. D., O'Connor, P. J., Crabbe, J. B., and Dishman, R. K. Acute exercise reduces caffeine-induced anxiogenesis. Med.Sci Sports Exerc. 1998;30(5):740-745. PubMed
- Kaminsky, L. A., Martin, C. A., and Whaley, M. H. Caffeine consumption habits do not influence the exercise blood pressure response following caffeine ingestion. J.Sports Med.Phys.Fitness 1998;38(1):53-58.
- McManamy, M. C. and Schube, P. G. Caffeine intoxication: report of a case the symptoms of which amounted to a psychosis. New England Journal of Medicine 1936;215:616-620. DOI
- Richter, J. E., Katz, P. O., and Waring, J. P. Gastroesophageal Reflux Disease. IFFGD 2000;
- Hsu, C., Harden, R. N., and Houle, T. Nicotine and caffeine intake in complex regional pain syndrome. Journal of Back and Musculoskeletal Rehabilitation 2002;16(1):33-38. PubMed
- Luebbe, A. M. Child and Adolescent Anxiety Sensitivity, Perceived Subjective Effects of Caffeine and Caffeine Consumption. J Caffeine Res 2011;1(4):213-218. DOI
- Li-Neng, Y., Greenstadt, L., and Shapiro, D. Effects of caffeine on blood pressure:A cross-cultural comparison. Psychophysiology 1983;20
- Fotherby, M. D., Ghandi, C., Haigh, R. A., Macdonald, T. A., and Potter, J. F. Sustained caffeine use has no pressor effect in the elderly. Cardiology in the Elderly 1994;2(6):499-503.
- Basurto Ona X, Uriona Tuma SM, Martínez García L, Solà I, Bonfill Cosp X. Drug therapy for preventing post-dural puncture headache. Cochrane Database Syst Rev. 2013 28;2:CD001792. doi: 10.1002/14651858.CD001792.pub3. Review. PubMed
- Beaudoin MS, Allen B, Mazzetti G, Sullivan PJ, Graham TE. Caffeine ingestion impairs insulin sensitivity in a dose-dependent manner in both men and women. Appl Physiol Nutr Metab. 2013;38(2):140-7. doi: 10.1139/apnm-2012-0201. Epub 2012 9. PubMed
- Caldeira D, Martins C, Alves LB, Pereira H, Ferreira JJ, Costa J. Caffeine does not increase the risk of atrial fibrillation: a systematic review and meta-analysis of observational studies. Heart. 2013;99(19):1383-9. doi: 10.1136/heartjnl-2013-303950. Re PubMed
- Chen L, Bell EM, Browne ML, Druschel CM, Romitti PA, Schmidt RJ, Burns TL, Moslehi R, Olney RS; National Birth Defects Prevention Study. Maternal caffeine consumption and risk of congenital limb deficiencies. Birth Defects Res A Clin Mol Teratol. 2012 De PubMed
- Chen LW, Wu Y, Neelakantan N, Chong MF, Pan A, van Dam RM. Maternal caffeine intake during pregnancy is associated with risk of low birth weight: a systematic review and dose-response meta-analysis. BMC Med. 2014 19;12:174. doi: 10.1186/s12916-014-0174-6 PubMed
- Cheng M, Hu Z, Lu X, Huang J, Gu D. Caffeine intake and atrial fibrillation incidence: dose response meta-analysis of prospective cohort studies. Can J Cardiol. 2014 Apr;30(4):448-54. doi: 10.1016/j.cjca.2013.12.026. Epub 2014 2. Review. PubMed
- Chiaffarino F, Bravi F, Cipriani S, Parazzini F, Ricci E, Viganò P, La Vecchia C. Coffee and caffeine intake and risk of endometriosis: a meta-analysis. Eur J Nutr. 2014 Oct;53(7):1573-9. doi: 10.1007/s00394-014-0662-7. Epub 2014 31. PubMed
- Greenwood DC, Thatcher NJ, Ye J, Garrard L, Keogh G, King LG, Cade JE. Caffeine intake during pregnancy and adverse birth outcomes: a systematic review and dose-response meta-analysis. Eur J Epidemiol. 2014;29(10):725-34. doi: 10.1007/s10654-014-9944-x. PubMed
- Jiang W, Wu Y, Jiang X. Coffee and caffeine intake and breast cancer risk: an updated dose-response meta-analysis of 37 published studies. Gynecol Oncol. 2013 Jun;129(3):620-9. doi: 10.1016/j.ygyno.2013.03.014. Epub 2013 25. Review. PubMed
- Lee SM, Choi NK, Lee BC, Cho KH, Yoon BW, Park BJ. Caffeine-containing medicines increase the risk of hemorrhagic stroke. Stroke. 2013 Aug;44(8):2139-43. doi: 10.1161/STROKEAHA.111.674077. Epub 2013 6. PubMed
- Sanikini H, Dik VK, Siersema PD, Bhoo-Pathy N, Uiterwaal CS, Peeters PH, González CA, Zamora-Ros R, Overvad K, Tjønneland A, Roswall N, Boutron-Ruault MC, Fagherazzi G, Racine A, Kühn T, Katzke V, Boeing H, Trichopoulou A, Trichopoulos D, Lagiou P, Palli
- Simonin C, Duru C, Salleron J, Hincker P, Charles P, Delval A, Youssov K, Burnouf S, Azulay JP, Verny C, Scherer C, Tranchant C, Goizet C, Debruxelles S, Defebvre L, Sablonnière B, Romon-Rousseaux M, Buée L, Destée A, Godefroy O, Dürr A, Landwehrmeyer B;
- Szpak A, Allen D. A case of acute suicidality following excessive caffeine intake. J Psychopharmacol. 2012 Nov;26(11):1502-10. doi: 10.1177/0269881112442788. Epub 2012 2. PubMed
- van der Hoeven N, Visser I, Schene A, van den Born BJ. Severe hypertension related to caffeinated coffee and tranylcypromine: a case report. Ann Intern Med. 2014 May 6;160(9):657-8. doi: 10.7326/L14-5009-8. No abstract available. PubMed
- Dixit S, Stein PK, Dewland TA, Dukes JW, Vittinghoff E, Heckbert SR, Marcus GM. Consumption of Caffeinated Products and Cardiac Ectopy. J Am Heart Assoc. 2016 26;5(1). pii: e002503. doi: 10.1161/JAHA.115.002503. PubMed
- Sheppard SG. A preliminary investigation of ibogaine: case reports and recommendations for further study. J Subst Abuse Treat. 1994 Jul-Aug;11(4):379-85. PubMed
- Zuchinali P, Riberio PA, Pimentel M, da Rosa PR, Zimerman LI, Rohde LE. Effect of caffeine on ventricular arrhythmia: a systematic review and meta-analysis of experimental and clinical studies. Europace 2016 Feb;18(2):257-66. PubMed
- Rhee J, Kim R, Kim Y, et al. Maternal caffeine consumption during pregnancy and risk of low birth weight: a dose-response meta-analysis of observational studies. PLoS One. 2015 Jul 20;10(7):e0132334. PubMed
- Zuchinali P, Souza GC, Pimentel M, et al. Short-term effects of high-dose caffeine on cardiac arrhythmias in patients with heart failure: a randomized clinical trial. JAMA Intern Med. 2016 Dec 1;176(12):1752-59. PubMed
- Lystrup RM, Leggit JC. Caffeine toxicity due to supplement use in caffeine - naïve individual: a cautionary tale. Mil Med. 2015 Aug;180(8):e936-40. PubMed
- Magdalan J, Zawadzki M, Skowronek R, et al. Nonfatal and fata intoxications with pure caffeine - report of three different cases. Forensic Sci Med Pathol. 2017 Sep;13(3):355-58.
- Trexler ET, Smith-Ryan AE, Roelofs EJ, Hirsch KR, Persky AM, Mock AG. Effects of coffee and caffeine anhydrous intake during creatine loading. J Strength Cond Res. 2016 May;30(5):1438-46. PubMed
- Lagier D, Nee L, Guieu R, et al. Peri-operative oral caffeine does not prevent postoperative atrial fibrillation after heart valve surgery with cardiopulmonary bypass: a randomized controlled clinical trial. Eur J Anaesthesiol. 2018 Apr 26. [Epub ahead of DOI
- Voskoboinik A, Kalman JM, Kistler PM. Caffeine and arrhythmias: time to grind the data. JACC: Clin Electrophysiol. 2018;4(4):425-32. PubMed
- Wang HR, Woo YS, Bahk WM. Caffeine-induced psychiatric manifestations: a review. Int Clin Psychopharmacol. 2015 Jul;30(4):179-82. PubMed
- Wikoff D, Welsh BT, Henderson R, et al. Systematic review of the potential adverse effects of caffeine consumption in healthy adults, pregnant women, adolescents, and children. Food Chem Toxicol 2017;109:585-648. PubMed
- Vliegenthart R, Miedema M, Hutten GJ, van Kaam AH, Onland W. High versus standard dose caffeine for apnoea: a systematic review. Arch Dis Child Fetal Neonatal Ed 2018;103(6):F523-9. doi: 10.1136/archdischild-2017-313556. PubMed
- Modzelewska D, Bellocco R, Elfvin A, et al. Caffeine exposure during pregnancy, small for gestational age birth and neonatal outcome - results from the Norwegian Mother and Child Cohort Study. BMC Pregnancy Childbirth. 2019;19(1):80. PubMed
- Shen JG, Brooks MB, Cincotta J, Manjourides JD. Establishing a relationship between the effect of caffeine and duration of endurance athletic time trial events: A systematic review and meta-analysis. J Sci Med Sport. 2019;22(2):232-238. PubMed
- Berglundh S, Vollrath M, Brantsæter AL, et al. Maternal caffeine intake during pregnancy and child neurodevelopment up to eight years of age-Results from the Norwegian Mother, Father and Child Cohort Study. Eur J Nutr. 2020. PubMed
- Jin F, Qiao C. Association of maternal caffeine intake during pregnancy with low birth weight, childhood overweight, and obesity: a meta-analysis of cohort studies. Int J Obes (Lond). 2020. PubMed
- Krittanawong C, Tunhasiriwet A, Wang Z, et al. Is caffeine or coffee consumption a risk for new-onset atrial fibrillation? A systematic review and meta-analysis. Eur J Prev Cardiol. 2020:2047487320908385. PubMed
- Zhang H, Lee ZX, Qiu A. Caffeine intake and cognitive functions in children. Psychopharmacology (Berl). 2020;237(10):3109-3116. PubMed
- Stojanovic E, Scanlan AT, Milanovic Z, Fox JL, Stankovic R, Dalbo VJ. Acute caffeine supplementation improves jumping, sprinting, and change-of-direction performance in basketball players when ingested in the morning but not evening. Eur J Sport Sci. 2021 PubMed
- Zheng KH, Zhu K, Wactawski-Wende J, et al. Caffeine intake from coffee and tea and invasive breast cancer incidence among postmenopausal women in the Women's Health Initiative. Int J Cancer 2021;149(12):2032-2044. PubMed
- Wang S, Li X, Yang Y, et al. Does coffee, tea and caffeine consumption reduce the risk of incident breast cancer? A systematic review and network meta-analysis. Public Health Nutr 2021;24(18):6377-6389. PubMed
- Alshabi AM, Alkahtani SA, Shaikh IA, Habeeb MS. Caffeine modulates pharmacokinetic and pharmacodynamic profiles of pioglitazone in diabetic rats: Impact on therapeutics. Saudi Med J 2021;42(2):151-160. PubMed
- Hinkle SN, Gleason JL, Yisahak SF, et al. Assessment of Caffeine Consumption and Maternal Cardiometabolic Pregnancy Complications. JAMA Netw Open 2021;4(11):e2133401. PubMed
- Yartsev A, Peisah C. Caffeine-clozapine interaction associated with severe toxicity and multiorgan system failure: a case report. BMC Psychiatry 2021;21(1):192. PubMed
- Tinawi M. Severe Rhabdomyolysis Due to Strenuous Exercise With a Potential Role of a High-Caffeine Energy Drink. Cureus 2022;14(1):e20867. PubMed
- Gleason JL, Sundaram R, Mitro SD, et al. Association of maternal caffeine consumption during pregnancy with child growth. JAMA Netw Open. 2022;5(10):e2239609. PubMed
- Ismail RIH, Awad HA, Saber M, Shehata BM. Bone mineral content for preterm neonates treated with caffeine using dual energy X-ray absorptiometry: An observational study. J Neonatal Perinatal Med 2023;16(1):129-135. PubMed
- Zhao J, Huang Y, Yu X. Caffeine intake and the risk of incident kidney stones: a systematic review and meta-analysis. Int Urol Nephrol 2022;54(10):2457-2466. PubMed
- Abbas-Hashemi SA, Hosseininasab D, Rastgoo S, Shiraseb F, Asbaghi O. The effects of caffeine supplementation on blood pressure in adults: A systematic review and dose-response meta-analysis. Clin Nutr ESPEN 2023;58:165-177. PubMed
- Oliphant EA, Hanning SM, McKinlay CJD, Alsweiler JM. Caffeine for apnea and prevention of neurodevelopmental impairment in preterm infants: systematic review and meta-analysis. J Perinatol 2024;44(6):785-801. PubMed
- Kühne T, Wallace E, Herzig D, et al. Combined intake of caffeine and low-dose glucose to reduce exercise-related hypoglycaemia in individuals with type 1 diabetes on ultra-long-acting insulin degludec: A randomized, controlled, double-blind, cross-over tr
- Song JJ, Eyabi JC, Awatramani PD, Mitchell BG, Nene SY. Sudden Reduction in Caffeine Intake Increases Serum Lithium Concentration to Supratherapeutic Level: A Case Report. Prim Care Companion CNS Disord 2024;26(2):23cr03642. PubMed
Chaga 9 references
- Sun JE, Ao ZH, Lu ZM, et al. Antihyperglycemic and antilipidperoxidative effects of dry matter of culture broth of Inonotus obliquus in submerged culture on normal and alloxan-diabetes mice. J Ethnopharmacol 2008;118(1):7-13. PubMed
- Hyun KW, Jeong SC, Lee DH, et al. Isolation and characterization of a novel platelet aggregation inhibitory peptide from the medicinal mushroom, Inonotus obliquus. Peptides 2006;27(6):1173-8. PubMed
- Kim YO, Han SB, Lee HW, et al. Immuno-stimulating effect of the endo-polysaccharide produced by submerged culture of Inonotus obliquus. Life Sci 2005;77(19):2438-56. PubMed
- Kikuchi Y, Seta K, Ogawa Y, et al. Chaga mushroom-induced oxalate nephropathy. Clin Nephrol 2014;81(6):440-4. PubMed
- Lee S, Lee HY, Park Y, et al. Development of end stage renal disease after long-term ingestion of chaga mushroom: case report and review of literature. J Korean Med Sci. 2020;35(19):e122.
- Kwon O, Kim Y, Paek JH, et al. Chaga mushroom-induced oxalate nephropathy that clinically manifested as nephrotic syndrome: A case report. Medicine (Baltimore) 2022;101(10):e28997. PubMed
- Su L, Xin C, Yang J, et al. A polysaccharide from Inonotus obliquus ameliorates intestinal barrier dysfunction in mice with type 2 diabetes mellitus. Int J Biol Macromol 2022;214:312-323. PubMed
- Chen S, Ma Y, Li H, et al. Anti-diabetic e?ects of Inonotus obliquus extract in high fat diet combined streptozotocin-induced type 2 diabetic mice. Nutr Hosp 2022;39(6):1256-1263. PubMed
- Ye X, Wu K, Xu L, et al. Methanol extract of Inonotus obliquus improves type 2 diabetes mellitus through modifying intestinal flora. Front Endocrinol (Lausanne) 2023;13:1103972. PubMed
Apple Cider Vinegar 11 references
- Lhotta K, Hofle G, Gasser R, Finkenstedt G. Hypokalemia, hyperreninemia, and osteoporosis in a patient ingesting large amounts of cider vinegar. Nephron 1998;80:242-3. PubMed
- Hill LL, Woodruff LH, Foote JC, Barreto-Alcoba M. Esophageal injury by apple cider vinegar tablets and subsequent evaluation of products. J Am Diet Assoc 2005;105:1141-4. PubMed
- Hlebowicz J, Darwiche G, Björgell O, Almér LO. Effect of apple cider vinegar on delayed gastric emptying in patients with type 1 diabetes mellitus: a pilot study. BMC Gastroenterol 2007;7:46. PubMed
- Johnston CS, Kim CM, Buller AJ. Vinegar improves insulin sensitivity to a high-carbohydrate meal in subjects with insulin resistance or type 2 diabetes. Diabetes Care 2004;27:281-2. PubMed
- Lhotta, K., Hofle, G., Gasser, R., and Finkenstedt, G. Hypokalemia, hyperreninemia and osteoporosis in a patient ingesting large amounts of cider vinegar. Nephron 1998;80(2):242-243. PubMed
- Bunick CG, Lott JP, Warren CB, et al. Chemical burn from topical apple cider vinegar. J Am Acad Dermatol 2012;67(4):e143-4. PubMed
- Feldstein S, Afshar M, Krakowski AC. Chemical Burn from Vinegar Following an Internet-based Protocol for Self-removal of Nevi. J Clin Aesthet Dermatol. 2015 Jun;8(6):50.
- Luu LA, Flowers RH, Kellams AL, et al. Apple cider vinegar soaks [0.5%] as a treatment for atopic dermatitis do not improve skin barrier integrity. Pediatr Dermatol. 2019;36(5):634-639. PubMed
- Hadi A, Pourmasoumi M, Najafgholizadeh A, Clark CCT, Esmaillzadeh A. The effect of apple cider vinegar on lipid profiles and glycemic parameters: a systematic review and meta-analysis of randomized clinical trials. BMC Complement Med Ther 2021;21(1):179. PubMed
- Feise NK, Johnston CS. Commercial vinegar tablets do not display the same physiological benefits for managing postprandial glucose concentrations as liquid vinegar. J Nutr Metab 2020;2020:9098739. PubMed
- Gheflati A, Bashiri R, Ghadiri-Anari A, Reza JZ, Kord MT, Nadjarzadeh A. The effect of apple vinegar consumption on glycemic indices, blood pressure, oxidative stress, and homocysteine in patients with type 2 diabetes and dyslipidemia: A randomized contro
Turkey Tail Mushroom 15 references
- Nakazato H, Koike A, Saji S, et al. Efficacy of immunochemotherapy as adjuvant treatment after curative resection of gastric cancer. Study Group of Immunochemotherapy with PSK for Gastric Cancer. Lancet 1994;343:1122-6. PubMed
- Mitomi T, Tsuchiya S, Iijima N, et al. Randomized, controlled study on adjuvant immunochemotherapy with PSK in curatively resected colorectal cancer. The Cooperative Study Group of Surgical Adjuvant Immunochemotherapy for Cancer of Colon and Rectum (Kanag DOI
- Torisu M, Hayashi Y, Ishimitsu T, et al. Significant prolongation of disease-free period gained by oral polysaccharide K (PSK) administration after curative surgical operation of colorectal cancer. Cancer Immunol Immunother 1990;31:261-8. PubMed
- Tsujitani, S., Kakeji, Y., Orita, H., Watanabe, A., Kohnoe, S., Baba, H., Anai, H., Maehara, Y., and Sugimachi, K. Postoperative adjuvant immunochemotherapy and infiltration of dendritic cells for patients with advanced gastric cancer. Anticancer Res 199
- Kojima, J., Kamata, T., and Monna, T. [Evaluation of immunochemotherapy in patients with primary liver cancer. Osaka Research Society for Liver, Gallbladder and Pancreas]. Gan To Kagaku Ryoho 1987;14(1):179-187.
- Fukuo, Y., Terashi, A., Hayashi, Y., Yano, Y., and Atarashi, J. [A clinical trial of cis-platinum (II) in combination with PSK and FT-207 in advanced stomach cancer]. Gan To Kagaku Ryoho 1985;12(4):960-965.
- Imaizumi, M., Kondo, T., Kamei, H., and Ichihashi, H. [Cooperative studies on surgical adjuvant immunochemotherapy for prevention of postoperative recurrence of gastric cancer]. Gan To Kagaku Ryoho 1984;11(1):60-68.
- Yeung JH and Or PM. Polysaccharide peptides from Coriolus versicolor competitively inhibit tolbutamide 4-hydroxylation in specific human CYP2C9 isoform and pooled human liver microsomes. Phytomedicine 2011;18(13):1170-5. PubMed
- Eliza WL, Fai CK, Chung LP. Efficacy of Yun Zhi (Coriolus versicolor) on survival in cancer patients: systematic review and meta-analysis. Recent Pat Inflamm Allergy Drug Discov 2012;6(1):78-87. PubMed
- Chan SL, Yeung JH. Effects of polysaccharide peptide (PSP) from Coriolus versicolor on the pharmacokinetics of cyclophosphamide in the rat and cytotoxicity in HepG2 cells. Food Chem Toxicol 2006;44:689-94. PubMed
- Serrano L, López AC, González SP, et al. Efficacy of a Coriolus versicolor-based vaginal gel in women with human papillomavirus-dependent cervical lesions: The PALOMA study. J Low Genit Tract Dis 2021;25(2):130-136. PubMed
- Meng F, Lin Y, Hu L, Feng W, Su P, Wu L. The therapeutic effect of Coriolus versicolor fruiting body on STZ-induced ICR diabetic mice. J Healthc Eng 2022;2022:7282453. PubMed
- Razmovski-Naumovski V, Kimble B, Laurenti D, Nammi S, Norimoto H, Chan K. Polysaccharide peptide extract from Coriolus versicolor increased T(max) of tamoxifen and maintained biochemical serum parameters, with no change in the metabolism of tamoxifen in t
- Cortés Bordoy J, de Santiago García J, Agenjo González M, et al. Effect of a multi-ingredient Coriolus-versicolor-based vaginal gel in women with HPV-dependent cervical lesions: The papilobs real-life prospective study. Cancers (Basel) 2023;15(15):3863. PubMed
- Nikolic M, Lazarevic N, Novakovic J, et al. Characterization, in vitro biological activity and in vivo cardioprotective properties of Trametes versicolor (L.:Fr.) quél. heteropolysaccharides in a rat model of metabolic syndrome. Pharmaceuticals (Basel) 20 PubMed
See these in context on the Turkey Tail Mushroom monograph →
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC