
Liver Defend Ingredients & Drug Interactions
by NuMedica
What is this page for?
First and foremost: checking Liver Defend against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Liver Defend is a dietary supplement by NuMedica with 4 active ingredients. Its ingredients are commonly taken for thyroid health support, antioxidant support, immune support.Based on those ingredients, 1,297 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Milk Thistle Seed Extract, Selenium, N-Acetyl L-Cysteine. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Liver Defend by NuMedica
Ask about any prescription or over-the-counter medication and we check it for interactions with Liver Defend by NuMedica — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Liver Defend by NuMedica
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
Liver Defend contains four active ingredients. Selenium is a mineral that your body needs in small amounts for thyroid and immune function.
Alpha-lipoic acid is an antioxidant compound your cells make naturally and that may support energy production. N-acetyl cysteine (or NAC) is a form of the amino acid cysteine that supports your body's production of glutathione, a major antioxidant.
Milk thistle seed extract contains silymarin, a plant compound traditionally used to support liver health. The product also contains inactive ingredients (hydroxypropylmethylcellulose, magnesium stearate, and bamboo silica) that serve as capsule material and flow agents.
Does it work?
Strong evidence
The evidence varies by ingredient and intended use. Selenium is likely effective for selenium deficiency and possibly effective for Kashin-Beck disease (a bone and joint condition), pre-eclampsia, and autoimmune thyroiditis — though it's rated possibly ineffective for high cholesterol.
Alpha-lipoic acid is possibly effective for diabetic nerve damage and possibly effective for high cholesterol and weight management. N-acetyl cysteine is effective for acetaminophen poisoning, atelectasis (collapsed lung tissue), and tracheostomy care, and is possibly effective for bronchitis.
Milk thistle is possibly effective for type 2 diabetes, but for most other conditions we hold — such as liver disease, hay fever, and mushroom poisoning — the evidence is not established in our data.
How safe is it?
Well-documented data
Selenium is generally well tolerated in small recommended amounts, but excess can be toxic; avoid high-dose supplements unless your doctor advises otherwise. Alpha-lipoic acid is generally well tolerated at typical doses but can lower blood sugar — use it under medical guidance — and the safety data advises against it during pregnancy and breastfeeding.
N-acetyl cysteine is generally well tolerated at typical doses (most side effects occur above 9 grams per dose or 30 grams daily); talk to your healthcare provider before use, and there isn't enough data to know if it's safe in pregnancy — discuss with your doctor. Milk thistle is generally well tolerated in most adults; however, the safety data advises against it during pregnancy, and caution is advised while breastfeeding since it's not well studied there.
The most common side effects across these ingredients are mild gastrointestinal symptoms (nausea, diarrhea, heartburn, bloating).
Meds to double-check
Major interaction found
Before taking Liver Defend, double-check any of these with your pharmacist: nitroglycerin or other heart medications (Major risk), blood thinners or antiplatelet drugs, blood pressure medications, antidiabetes drugs, warfarin, chemotherapy drugs, thyroid hormone medications, barbiturates, immunosuppressants, and morphine or other opioids. These carry Moderate-severity interactions with one or more of the four ingredients.
The bottom line
Scorecard at a glanceFully disclosed formula with clinical evidence supporting its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
Liver Defend is a four-ingredient supplement aimed at liver support, but it carries multiple drug interactions — especially with blood thinners, heart medications, blood pressure drugs, and chemotherapy. If you take any prescription medication, blood thinner, or blood pressure med, check your exact drugs with the tool on this page before starting.
Talk with your pharmacist or doctor to see if it fits your situation.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 4 of 4 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jan 23, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Liver Defend, straight from the product label.
| Brand | NuMedica |
|---|---|
| Barcode (UPC) | 812527010734 |
| Net contents | 60 Vegetable Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Jan 23, 2025 |
| DSLD ID | 323565 |
| Product type | Other Combinations |
| Supplement form | Capsule |
| Dietary claims / uses | Nutrient, All Other, Structure/Function |
| Intended target group(s) | Vegan, Vegetarian, Adult (18 - 50 Years), Gluten Free, Dairy Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
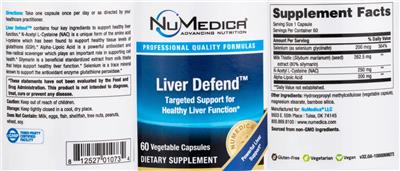
Supplement Facts
The label details for Liver Defend by NuMedica, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Selenium | 200 mcg | 364% |
| Alpha-Lipoic Acid | 200 mg | -- |
| N-Acetyl L-Cysteine | 250 mg | -- |
| Milk Thistle Seed Extract | 262.5 mg | -- |
Other ingredients: Hydroxypropylmethylcellulose, Magnesium Stearate, Bamboo Silica
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Suggested/Recommended/Usage/Directions
Directions: Take one capsule once per day or as directed by your healthcare practitioner.
Formulation
Liver Defend contains four key ingredients to support healthy liver function.
Does not contain: Milk, eggs, fish, shellfish, tree nuts, peanuts, wheat, soy.
Professional Quality Formulas
Targeted support for healthy liver function Powerful Liver Support
Sourced from non-GMO ingredients. Gluten-Free
Vegetarian Vegan
Formula
N-Acetyl L-Cycteine (NAC) is a unique form of the amino acid l-cysteine which has been found to support healthy tissue levels of glutathione (GSH). Alpha-Lipoic Acid is a powerful antioxidant and free-radical scavenger which plays an important role in supporting cell health. Silymarin is a beneficial standardized extract from milk thistle that helps support healthy liver function. Selenium is a trace mineral known to support the antioxidant enzyme glutathione peroxidase.
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure or prevent any disease.
Precautions
Caution: Keep out of reach of children.
Storage
Storage: Keep tightly closed in a cool, dry place.
Seals/Symbols
cGMP Third-Party Certified Facility
Brand IP Statement(s)
NuMedica Advancing Nutrition
FDA Statement of Identity
Dietary Supplement
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Liver Defend by NuMedica label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Liver Defend by NuMedica
These are the 4 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Capsule(s) Dosage formCapsule Servings per container60 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Selenium
Interacts with321 drugs
Selenium is an essential trace mineral your body needs in small amounts for thyroid function, antioxidant defense, and immune health. Most people who...
Selenium monograph & interactionsAlpha-Lipoic Acid
Interacts with263 drugs
Alpha-lipoic acid (ALA) is an antioxidant made naturally by the body and found in small amounts in foods. It is most studied for diabetic nerve pain,...
Alpha-Lipoic Acid monograph & interactionsN-Acetyl L-Cysteine
Interacts with294 drugs
N-acetyl cysteine (NAC) is a supplement form of the amino acid cysteine and a building block for the antioxidant glutathione. It has well-established...
N-Acetyl L-Cysteine monograph & interactionsMilk Thistle Seed Extract
Interacts with954 drugs
Milk thistle is a popular herbal supplement most often used for liver health, and its main active component is a group of compounds called silymarin....
Milk Thistle Seed Extract monograph & interactionsOther (inactive) ingredients: Hydroxypropylmethylcellulose, Magnesium Stearate, Bamboo Silica. These complete the product’s ingredient list but are not active constituents.
Liver Defend by NuMedica Drug Interactions
HelloPharmacist Interaction Report
Liver Defend by NuMedica contains four active ingredients that interact with multiple medication types.
The most serious interaction involves N-acetyl cysteine with nitroglycerin (a heart medication), which can cause severe drops in blood pressure and severe headaches — this is a Major-severity concern and requires you to talk with your doctor or pharmacist before combining them.
Read the full breakdown — every affected drug type, severity by severity
Selenium interacts with blood thinners and antiplatelet drugs (Moderate severity), raising bleeding risk. It may also reduce how well immunosuppressants work, prolong the sedating effects of barbiturates, and interfere with warfarin activity — all Moderate.
Alpha-lipoic acid similarly affects blood thinners and antiplatelet drugs (Moderate), and may interfere with chemotherapy drugs, thyroid hormone medications, and antidiabetes drugs.
N-acetyl cysteine also carries Moderate interactions with blood pressure medications (risk of low blood pressure), blood thinners, and chloroquine (an antimalarial). Milk thistle has the broadest range: Moderate interactions with multiple drug types including antidiabetes drugs (risk of low blood sugar), warfarin, morphine, several chemotherapy-related drugs, and others that depend on liver metabolism.
Altogether, these interactions span 1,279 individual medications.
Run your exact medications through the interaction checker below before starting this product.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Liver Defend?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Liver Defend interact with 1,297 drugs. Click any drug to see the details.
4 of the 4 ingredients in Liver Defend interact with drugs. Each result below shows which ingredient is responsible. Milk Thistle Seed Extract Selenium N-Acetyl L-Cysteine Alpha-Lipoic Acid
NitroglycerinGonitro, Nitro Time, Nitro-Bid, Nitrocine Timecaps, Nitrogard, Nitrogard SR +7 more
How Nitroglycerin interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
N-acetyl L-cysteineNitroglycerin Major
Interaction Summary
N-acetyl cysteine can increase the risk for hypotension and headaches when taken with intravenous or transdermal nitroglycerin.
Read the full N-acetyl L-cysteine + Nitroglycerin interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
SeleniumImmunosuppressants Moderate
Interaction Summary
Theoretically, selenium supplementation may reduce the effectiveness of immunosuppressant therapy.
Read the full Selenium + 6-mercaptopurine interactionAbciximabReoPro
How Abciximab interacts with Liver Defend — through 3 ingredients. Tap an ingredient for the detail:
SeleniumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Selenium + Abciximab interactionN-acetyl L-cysteineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, N-acetyl cysteine might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full N-acetyl L-cysteine + Abciximab interactionAlpha-lipoic AcidAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Alpha-lipoic Acid + Abciximab interactionAbrocitinibCibinqo
How Abrocitinib interacts with Liver Defend — through 4 ingredients. Tap an ingredient for the detail:
N-acetyl L-cysteineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, N-acetyl cysteine might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full N-acetyl L-cysteine + Abrocitinib interactionSeleniumImmunosuppressants, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, selenium supplementation may reduce the effectiveness of immunosuppressant therapy.
Read the full Selenium + Abrocitinib interactionAlpha-lipoic AcidAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Alpha-lipoic Acid + Abrocitinib interactionMilk Thistle Seed ExtractCytochrome P450 2c9 (cyp2c9) Substrates Minor
Interaction Summary
It is unclear if milk thistle inhibits CYP2C9; research is conflicting.
Read the full Milk Thistle Seed Extract + Abrocitinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Liver Defend — through 2 ingredients. Tap an ingredient for the detail:
Milk Thistle Seed ExtractAntidiabetes Drugs Moderate
Interaction Summary
Taking milk thistle with antidiabetes drugs may increase the risk of hypoglycemia.
Read the full Milk Thistle Seed Extract + Acarbose interactionAlpha-lipoic AcidAntidiabetes Drugs Minor
Interaction Summary
Theoretically, taking alpha-lipoic acid with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Alpha-lipoic Acid + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
N-acetyl L-cysteineAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, N-acetyl cysteine might increase the risk of hypotension when taken with antihypertensive drugs.
Read the full N-acetyl L-cysteine + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Liver Defend — through 3 ingredients. Tap an ingredient for the detail:
SeleniumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Selenium + Acenocoumarol interactionAlpha-lipoic AcidAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Alpha-lipoic Acid + Acenocoumarol interactionN-acetyl L-cysteineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, N-acetyl cysteine might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full N-acetyl L-cysteine + Acenocoumarol interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with Liver Defend — through 4 ingredients. Tap an ingredient for the detail:
N-acetyl L-cysteineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, N-acetyl cysteine might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full N-acetyl L-cysteine + Acetaminophen, Aspirin interactionSeleniumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Selenium + Acetaminophen, Aspirin interactionMilk Thistle Seed ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Aspirin interactionAlpha-lipoic AcidAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Alpha-lipoic Acid + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with Liver Defend — through 4 ingredients. Tap an ingredient for the detail:
Alpha-lipoic AcidAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Alpha-lipoic Acid + Acetaminophen, Aspirin, Caffeine interactionN-acetyl L-cysteineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, N-acetyl cysteine might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Read the full N-acetyl L-cysteine + Acetaminophen, Aspirin, Caffeine interactionMilk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Acetaminophen, Aspirin, Caffeine interactionSeleniumAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Selenium + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, ButalbitalAxocet, Bancap, Bucet, Butex Forte, Esgic CF, Orbivan CF +5 more
How Acetaminophen, Butalbital interacts with Liver Defend — through 2 ingredients. Tap an ingredient for the detail:
SeleniumBarbiturates Moderate
Interaction Summary
Theoretically, selenium might prolong the sedating effects of barbiturates.
Read the full Selenium + Acetaminophen, Butalbital interactionMilk Thistle Seed ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Butalbital interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with Liver Defend — through 2 ingredients. Tap an ingredient for the detail:
Milk Thistle Seed ExtractGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Butalbital, Caffeine interactionSeleniumBarbiturates Moderate
Interaction Summary
Theoretically, selenium might prolong the sedating effects of barbiturates.
Read the full Selenium + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with Liver Defend — through 2 ingredients. Tap an ingredient for the detail:
SeleniumBarbiturates Moderate
Interaction Summary
Theoretically, selenium might prolong the sedating effects of barbiturates.
Read the full Selenium + Acetaminophen, Butalbital, Caffeine, Codeine interactionMilk Thistle Seed ExtractGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractGlucuronidated Drugs Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Caffeine, IsomethepteneMigralam
How Acetaminophen, Caffeine, Isometheptene interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Caffeine, Isometheptene interactionAcetaminophen, Caffeine, PyrilamineMidol Max Strength Menstrual
How Acetaminophen, Caffeine, Pyrilamine interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Acetaminophen, Caffeine, Pyrilamine interactionAcetaminophen, Chlorpheniramine Maleate, Dextromethorphan HbrVicks Formula 44M Cough, Cold & Flu Relief
How Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionAcetaminophen, Chlorpheniramine, DextromethorphanCoricidin II Extra Strength Cold and Flu
How Acetaminophen, Chlorpheniramine, Dextromethorphan interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionAcetaminophen, Chlorpheniramine, Dextromethorphan HydrobromideCoricidin HBP Maximum Strength Flu
How Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionAcetaminophen, Chlorpheniramine, Dextromethorphan, PhenylpropanolamineMulti Symptom Cold Relief
How Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionAcetaminophen, Chlorpheniramine, Dextromethorphan, PseudoephedrineChildren's Tylenol Cold Plus Cough, Tylenol Cold Ex Strength
How Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interactionAcetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, SalicylamideRhinogesic GG
How Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractGlucuronidated Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Read the full Milk Thistle Seed Extract + Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interactionAcetaminophen, Chlorpheniramine, PhenylephrineAlka-Seltzer PLUS, Histex SR, Protid
How Acetaminophen, Chlorpheniramine, Phenylephrine interacts with Liver Defend — through 1 ingredient. Tap an ingredient for the detail:
Milk Thistle Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Glucuronidated Drugs Moderate
Interaction Summary
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
Read the full Milk Thistle Seed Extract + Acetaminophen, Chlorpheniramine, Phenylephrine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Liver Defend with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Milk Thistle Seed Extract
Antidiabetes Drugs
Taking milk thistle with antidiabetes drugs may increase the risk of hypoglycemia.
Clinical research shows that milk thistle extract, alone or along with tree turmeric extract, can lower blood glucose levels and glycated hemoglobin (HbA1c) in patients with type 2 diabetes, including those already taking antidiabetes drugs. Additionally, animal research shows that milk thistle extract increases the metformin maximum plasma concentration and area under the curve and decreases the renal clearance of metformin, due to inhibition of the multi-drug and toxin extrusion protein 1 (MATE1) renal tubular transport protein.
Cytochrome P450 2B6 (Cyp2B6) Substrates
Theoretically, milk thistle might inhibit CYP2B6.
An in vitro study shows that silybin, a constituent of milk thistle, binds to and noncompetitively inhibits CYP2B6. Additionally, silybin might downregulate the expression of CYP2B6 by decreasing mRNA and protein levels.
Glucuronidated Drugs
Theoretically, milk thistle might affect the clearance of drugs that undergo glucuronidation.
Laboratory research shows that milk thistle constituents inhibit uridine diphosphoglucuronosyl transferase (UGT), the major phase 2 enzyme that is responsible for glucuronidation. Theoretically, this could decrease the clearance and increase levels of glucuronidated drugs. Other laboratory research suggests that a milk thistle extract of silymarin might inhibit beta-glucuronidase, although the significance of this effect is unclear.
Ledipasvir
Theoretically, milk thistle might increase the levels and clinical effects of ledipasvir.
Animal research in rats shows that milk thistle increases the area under the curve (AUC) for ledipasvir and slows its elimination.
Morphine
Theoretically, concomitant use of milk thistle with morphine might affect serum levels of morphine and either increase or decrease its effects.
Animal research shows that milk thistle reduces serum levels of morphine by up to 66%. In contrast, laboratory research shows that milk thistle constituents inhibit uridine diphosphoglucuronosyl transferase (UGT), the major phase 2 enzyme that is responsible for glucuronidation. Theoretically, this could decrease the clearance and increase morphine levels. The effect of taking milk thistle on morphine metabolism in humans is not known.
Raloxifene (Evista)
Theoretically, milk thistle might decrease the clearance and increase levels of raloxifene.
Laboratory research suggests that the milk thistle constituents silibinin and silymarin inhibit the glucuronidation of raloxifene in the intestines.
Sirolimus (Rapamune)
Milk thistle might decrease the clearance of sirolimus.
Pharmacokinetic research shows that a milk thistle extract of silymarin decreases the apparent clearance of sirolimus in hepatically impaired renal transplant patients. It is unclear if this interaction occurs in patients without hepatic impairment.
Sofosbuvir (Solvaldi)
Theoretically, milk thistle might decrease the levels and clinical effects of sofosbuvir.
Animal research in rats shows that milk thistle reduces the metabolism of sofosbuvir, as well as the hepatic uptake of its active metabolite.
Tamoxifen (Nolvadex)
Theoretically, the milk thistle constituent silibinin might increase tamoxifen levels and interfere with its conversion to an active metabolite.
Animal research suggests that the milk thistle constituent silibinin might increase plasma levels of tamoxifen and alter its conversion to an active metabolite. The mechanism appears to involve inhibition of pre-systemic metabolism of tamoxifen by cytochrome P450 (CYP) 2C9 and CYP3A4, and inhibition of P-glycoprotein-mediated efflux of tamoxifen into the intestine for excretion. Whether this interaction occurs in humans is not known.
Warfarin (Coumadin)
Theoretically, milk thistle might increase the effects of warfarin.
In one case report, a man stabilized on warfarin experienced an increase in INR from 2.64 to 4.12 after taking a combination product containing milk thistle 200 mg daily, as well as dandelion, wild yam, niacinamide, and vitamin B12. Levels returned to normal after stopping the supplement. Although a direct correlation between milk thistle and the change in INR cannot be confirmed, some in vitro research suggests that milk thistle might inhibit cytochrome P450 2C9 (CYP2C9), an enzyme involved in the metabolism of various drugs, including warfarin.
Cytochrome P450 2C9 (Cyp2C9) Substrates
It is unclear if milk thistle inhibits CYP2C9; research is conflicting.
In vitro research suggests that milk thistle might inhibit CYP2C9. Additionally, 3 case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking milk thistle and cancer medications that are CYP2C9 substrates, including imatinib and capecitabine. However, contradictory clinical research shows that milk thistle extract does not inhibit CYP2C9 or significantly affect levels of the CYP2C9 substrate tolbutamide. Differences in results could be due to differences in dosages or formulations utilized.
Cytochrome P450 3A4 (Cyp3A4) Substrates
It is unclear if milk thistle inhibits CYP3A4; research is conflicting.
While laboratory research shows conflicting results, pharmacokinetic research shows that taking milk thistle extract 420-1350 mg daily does not significantly affect the metabolism of the CYP3A4 substrates irinotecan, midazolam, or indinavir. However, 8 case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking milk thistle and cancer medications that are CYP3A4 substrates, including gefitinib, sorafenib, doxorubicin, and vincristine.
Estrogens
Theoretically, milk thistle might interfere with estrogen therapy through competition for estrogen receptors.
Animal research suggests that a milk thistle extract of silymarin binds to estrogen receptor beta.
Hmg-Coa Reductase Inhibitors ("Statins")
Theoretically, milk thistle might interfere with statin therapy by decreasing the activity of organic anion transporting polypeptide 1B1 (OATB1B1) and inhibiting breast cancer resistance protein (BCRP).
Preliminary evidence suggests that a milk thistle extract of silymarin can decrease the activity of the OATP1B1, which transports HMG-CoA reductase inhibitors into the liver to their site of action, and animal research shows this increases the maximum plasma concentration of pitavastatin and pravastatin. The silibinin component also inhibits BCRP, which transports statins from the liver into the bile for excretion. However, in a preliminary study in healthy males, silymarin 140 mg three times daily had no effect on the pharmacokinetics of a single 10 mg dose of rosuvastatin.
Indinavir (Crixivan)
Theoretically, milk thistle may induce cytochrome P450 3A4 (CYP3A4) enzymes and increase the metabolism of indinavir; however, results are conflicting.
One pharmacokinetic study shows that taking milk thistle (Standardized Milk Thistle, General Nutrition Corp.) 175 mg three times daily in combination with multiple doses of indinavir 800 mg every 8 hours decreases the mean trough levels of indinavir by 25%. However, results from the same pharmacokinetic study show that milk thistle does not affect the overall exposure to indinavir. Furthermore, two other pharmacokinetic studies show that taking specific milk thistle extract (Legalon, Rottapharm Madaus; Thisilyn, Nature's Way) 160-450 mg every 8 hours in combination with multiple doses of indinavir 800 mg every 8 hours does not reduce levels of indinavir.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Milk thistle may inhibit one form of OATP, OATP-B1, which could reduce the bioavailability and clinical effects of OATP-B1 substrates.
In vitro research shows that milk thistle inhibits OATP-B1. Two case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking milk thistle and cancer medications that are OATP substrates, including sorafenib and methotrexate. OATPs are expressed in the small intestine and liver and are responsible for the uptake of drugs and other compounds into the body. Inhibition of OATP may reduce the bioavailability of oral drugs that are substrates of OATP.
P-Glycoprotein Substrates
Theoretically, milk thistle might increase the absorption of P-glycoprotein substrates. However, this effect does not seem to be clinically significant.
In vitro research shows that milk thistle can inhibit P-glycoprotein activity and 1 case report from the World Health Organization (WHO) adverse drug reaction database describes increased abdominal pain in a patient taking milk thistle and the cancer medication vincristine, a P-glycoprotein substrate, though this patient was also taking methotrexate. However, a small pharmacokinetic study in healthy volunteers shows that taking milk thistle (Enzymatic Therapy Inc.) 900 mg, standardized to 80% silymarin, in 3 divided doses daily for 14 days does not affect absorption of digoxin, a P-glycoprotein substrate.
Selenium
Anticoagulant/Antiplatelet Drugs
Selenium may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Clinical research suggests that taking selenium 10 mcg/kg/day can increase bleeding times by increasing prostacyclin production, which inhibits platelet activity. Other clinical research suggests that taking selenium 75 mcg daily, in combination with ascorbic acid 600 mg, alpha-tocopherol 300 mg, and beta-carotene 27 mg, reduces platelet aggregation.
Barbiturates
Theoretically, selenium might prolong the sedating effects of barbiturates.
Laboratory research suggests that selenium can inhibit the hepatic metabolism of barbiturates. Selenium seems to prolong the sedative effect of pentobarbital in animal models.
Immunosuppressants
Theoretically, selenium supplementation may reduce the effectiveness of immunosuppressant therapy.
In vitro research and preliminary clinical evidence suggests that selenium may stimulate the immune system.
Warfarin (Coumadin)
Theoretically, selenium might interfere with warfarin activity.
Animal research suggests that selenium can increase warfarin activity. Selenium might interact with warfarin by displacing it from albumin binding sites, reducing its metabolism in the liver, or by decreasing production of vitamin K-dependent clotting factors. Selenium can also prolong bleeding times in humans by increasing prostacyclin production, which inhibits platelet activity.
Contraceptive Drugs
Contraceptive drugs might increase levels of selenium, although the clinical significance of this effect is unclear.
Some research suggests that oral contraceptives increase serum selenium levels in women taking oral contraceptives; however, other research shows no change in selenium levels. It is suggested that an increase could be due to increased carrier proteins, indicating a redistribution of selenium rather than a change in total body selenium.
Niacin
Selenium might reduce the beneficial effects of niacin on high-density lipoprotein (HDL) levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as selenium, or to the combination. It also is not known whether it will occur in other patient populations.
N-Acetyl L-Cysteine
Nitroglycerin
N-acetyl cysteine can increase the risk for hypotension and headaches when taken with intravenous or transdermal nitroglycerin.
Clinical research shows that concomitant administration of N-acetyl cysteine and intravenous or transdermal nitroglycerin can cause severe hypotension and intolerable headaches. Furthermore, in vitro research suggests that N-acetyl cysteine increases the anticoagulant activity of nitroglycerin.
Activated Charcoal
N-acetyl cysteine might reduce the effects of activated charcoal, while activated charcoal might reduce the absorption of N-acetyl cysteine.
N-acetyl cysteine appears to reduce the capacity of activated charcoal to adsorb acetaminophen and salicylic acid. Conversely, although clinical research suggests that although activated charcoal can reduce the absorption of N-acetyl cysteine by up to 40%, it does not seem to reduce its clinical effects. Other clinical evidence suggests that activated charcoal does not affect the absorption of N-acetyl cysteine.
Anticoagulant/Antiplatelet Drugs
Theoretically, N-acetyl cysteine might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
Clinical research suggests that intravenous N-acetyl cysteine decreases prothrombin time, prolongs coagulation time, decreases platelet aggregation, and increases blood loss in surgical patients. Furthermore, in vitro research suggests that N-acetyl cysteine increases the anticoagulant activity of nitroglycerin.
Antihypertensive Drugs
Theoretically, N-acetyl cysteine might increase the risk of hypotension when taken with antihypertensive drugs.
Animal research suggests that N-acetyl cysteine potentiates the hypotensive effects of the angiotensin-converting enzyme inhibitors (ACEIs) captopril and enalaprilat. Theoretically, combining N-acetyl cysteine with other antihypertensive drugs might increase the risk of hypotension.
Chloroquine (Aralen)
Theoretically, N-acetyl cysteine might interfere with the antimalarial effects of chloroquine.
Animal research suggests that N-acetyl cysteine might reduce the antimalarial effects of chloroquine by increasing cellular levels of glutathione.
Alpha-Lipoic Acid
Alkylating Agents
Theoretically, the antioxidant effects of alpha-lipoic acid might alter the effectiveness of alkylating agents.
The use of antioxidants like alpha-lipoic acid during chemotherapy is controversial. There are concerns that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as alpha-lipoic acid have on chemotherapy. Advise patients to consult their oncologist before using alpha-lipoic acid.
Anticoagulant/Antiplatelet Drugs
Theoretically, alpha-lipoic acid may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro, alpha-lipoic acid inhibits platelet aggregation.
Antitumor Antibiotics
Theoretically, the antioxidant effects of alpha-lipoic acid might alter the effectiveness of antitumor antibiotics.
The use of antioxidants like alpha-lipoic acid during chemotherapy is controversial. There are concerns that antioxidants could reduce the activity of antitumor antibiotic drugs, which work by generating free radicals. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as alpha-lipoic acid have on chemotherapy involving antitumor antibiotics. Advise patients to consult their oncologist before using alpha-lipoic acid.
Thyroid Hormone
Theoretically, alpha-lipoic acid might decrease the effects of thyroid hormone drugs.
Animal research suggests that co-administration of thyroxine with alpha-lipoic acid reduces conversion into the active T3 form.
Antidiabetes Drugs
Theoretically, taking alpha-lipoic acid with antidiabetes drugs might increase the risk of hypoglycemia.
Although some small clinical studies have suggested that alpha-lipoic acid can lower blood glucose levels, larger clinical studies in patients with diabetes have shown no clinically meaningful effect. Additionally, co-administration of single doses of alpha-lipoic acid and glyburide or acarbose did not cause detectable drug interactions in healthy volunteers.
Brand information
Manufacturer and brand details for Liver Defend, from the product label.
NuMedica
See all NuMedica products- Name
- NuMedica LLC
- Street Address
- 9503 E. 55th Place
- City
- Tulsa
- State
- OK
- ZipCode
- 74145
- Phone Number
- 800.869.8100
- Web Address
- www.numedica.com
Liver Defend by NuMedica: Common Questions
Does Liver Defend by NuMedica interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take Liver Defend while pregnant?
Can I take Liver Defend while breastfeeding?
What are the most common side effects?
Does milk thistle in this product really help with liver health?
Can this product lower my blood sugar?
What happens if I take too much selenium from this product?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Liver Defend is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Liver Defend’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Selenium
Interacts with 321 drugsSelenium is an essential trace mineral your body needs in small amounts for thyroid function, antioxidant defense, and immune health. Most people who eat a varied diet get enough, and supple...
Read the full Selenium monograph → Herb & supplement monographAlpha-lipoic Acid
Interacts with 263 drugsAlpha-lipoic acid (ALA) is an antioxidant made naturally by the body and found in small amounts in foods. It is most studied for diabetic nerve pain, where some evidence suggests it may help...
Read the full Alpha-lipoic Acid monograph → Herb & supplement monographN-acetyl Cysteine (nac)
Interacts with 294 drugsN-acetyl cysteine (NAC) is a supplement form of the amino acid cysteine and a building block for the antioxidant glutathione. It has well-established prescription uses for acetaminophen over...
Read the full N-acetyl Cysteine (nac) monograph → Herb & supplement monographMilk Thistle
Interacts with 954 drugsMilk thistle is a popular herbal supplement most often used for liver health, and its main active component is a group of compounds called silymarin. While it is generally well tolerated, th...
Read the full Milk Thistle monograph →Sources & How We Checked
Liver Defend's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 239 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Selenium 36 references
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Trafikowska U, Zachara BA, Wiacek M, et al. Selenium supply and glutathione peroxidase activity in breastfed Polish infants. Acta Paediatr 1996;85:1143-5. PubMed
- Duffield-Lillico AJ, Slate EH, Reid ME, et al. Selenium supplementation and secondary prevention of nonmelanoma skin cancer in a randomized trial. J Natl Cancer Inst 2003;95:1477-81.. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Schiavon R, Freeman GE, Guidi GC, et al. Selenium enhances prostacyclin production by cultured endothelial cells: possible explanation for increased bleeding times in volunteers taking selenium as a dietary supplement. Thromb Res 1984;34:389-96. PubMed
- Davila JC, Edds GT, Osuna O, Simpson CF. Modification of the effects of aflatoxin B1 and warfarin in young pigs given selenium. Am J Vet Res 1983;44:1877-83. DOI
- Heese HD, Lawrence MA, Dempster WS, Pocock F. Reference concentrations of serum selenium and manganese in healthy nulliparas. S Afr Med J 1988;73:163-5.
- Lloyd B, Lloyd RS, Clayton BE. Effect of smoking, alcohol and other factors on the selenium status of a healthy population. J Epidemiol Commun Health 1983;37:213-7. PubMed
- Capel ID, Jenner M, Williams DC, et al. The effect of prolonged oral contraceptive steroid use on erythrocyte glutathione peroxidase activity. J Steroid Biochem 1981;14:729-32. PubMed
- Contempre B, Dumont JE, Ngo B, et al. Effect of selenium supplementation in hypothyroid subjects of an iodine and selenium deficient area: the possible danger of indiscriminate supplementation of iodine-deficient subjects with selenium. J Clin Endocrinol PubMed
- Hofbauer LC, Spitzweg C, Magerstadt RA, Heufelder AE. Selenium-induced thyroid dysfunction. Postgrad Med J 1997;73:103-4. PubMed
- Debski B, Milner JA. Dietary selenium supplementation prolongs pentobarbital induced hypnosis. J Nutr Biochem 2004;15:548-53. PubMed
- Ishikawa M, Sasaki M, Koiwai K, et al. Inhibition of hepatic mixed-function oxidase enzymes in mice by acute and chronic treatment with selenium. J Pharmacobiodyn 1992;15:377-85. PubMed
- Lippmann SM, Klein EA, Goodman PJ, et al. Effect of selenium and vitamin E on risk of prostate cancer and other cancers: the selenium and vitamin E cancer prevention trial (SELECT). JAMA 2009;301:39-51. DOI
- Reid SM, Middleton P, Cossich MC, Crowther CA. Interventions for clinical and subclinical hypothyroidism in pregnancy. Cochrane Database Syst Rev 2010;(7):CD007752. PubMed
- Vinceti, M., Wei, E. T., Malagoli, C., Bergomi, M., and Vivoli, G. Adverse health effects of selenium in humans. Rev.Environ.Health 2001;16(4):233-251. PubMed
- Abrams, C. K., Siram, S. M., Galsim, C., Johnson-Hamilton, H., Munford, F. L., and Mezghebe, H. Selenium deficiency in long-term total parenteral nutrition. Nutr Clin Pract 1992;7(4):175-178. PubMed
- Spiller, H. A. and Pfiefer, E. Two fatal cases of selenium toxicity. Forensic Sci Int 8-24-2007;171(1):67-72. PubMed
- Negro, R., Greco, G., Mangieri, T., Pezzarossa, A., Dazzi, D., and Hassan, H. The influence of selenium supplementation on postpartum thyroid status in pregnant women with thyroid peroxidase autoantibodies. J Clin Endocrinol.Metab 2007;92(4):1263-1268. PubMed
- Alexander, J. Selenium. Novartis.Found.Symp 2007;282:143-149.
- Salonen, J. T., Salonen, R., Seppanen, K., Rinta-Kiikka, S., Kuukka, M., Korpela, H., Alfthan, G., Kantola, M., and Schalch, W. Effects of antioxidant supplementation on platelet function: a randomized pair-matched, placebo-controlled, double-blind trial
- Kupka, R., Mugusi, F., Aboud, S., Msamanga, G. I., Finkelstein, J. L., Spiegelman, D., and Fawzi, W. W. Randomized, double-blind, placebo-controlled trial of selenium supplements among HIV-infected pregnant women in Tanzania: effects on maternal and chil
- Kamble, P., Mohsin, N., Jha, A., Date, A., Upadhaya, A., Mohammad, E., Khalil, M., Pakkyara, A., and Budruddin, M. Selenium intoxication with selenite broth resulting in acute renal failure and severe gastritis. Saudi.J Kidney Dis.Transpl. 2009;20(1):106
- Peretz, A., Neve, J., Desmedt, J., Duchateau, J., Dramaix, M., and Famaey, J. P. Lymphocyte response is enhanced by supplementation of elderly subjects with selenium-enriched yeast. Am.J Clin.Nutr. 1991;53(5):1323-1328. PubMed
- Kumpulainen, J., Salmenpera, L., Siimes, M. A., Koivistoinen, P., and Perheentupa, J. Selenium status of exclusively breast-fed infants as influenced by maternal organic or inorganic selenium supplementation. Am.J Clin.Nutr. 1985;42(5):829-835. PubMed
- Han, L. and Zhou, S. M. Selenium supplement in the prevention of pregnancy induced hypertension. Chin Med J (Engl) 1994;107(11):870-871.
- Kiremidjian-Schumacher, L., Roy, M., Wishe, H. I., Cohen, M. W., and Stotzky, G. Supplementation with selenium and human immune cell functions. II. Effect on cytotoxic lymphocytes and natural killer cells. Biol.Trace Elem.Res. 1994;41(1-2):115-127. PubMed
- Srivastava, A. K., Gupta, B. N., Bihari, V., and Gaur, J. S. Generalized hair loss and selenium exposure. Vet.Hum.Toxicol. 1995;37(5):468-469.
- Sudfeld CR, Aboud S, Kupka R, et al. Effect of selenium supplementation on HIV-1 RNA detection in breast milk of Tanzanian women. Nutrition 2014;30(9):1081-4. PubMed
- Rees K, Hartley L, Day C, et al. Selenium supplementation for the primary prevention of cardiovascular disease. Cochrane Database Syst Rev 2013;1:CD009671. PubMed
- Thompson PA, Ashbeck EL, Roe DJ, et al. Selenium Supplementation for Prevention of Colorectal Adenomas and Risk of Associated Type 2 Diabetes. J Natl Cancer Inst. 2016;108(12). PubMed
- Wichman J, Winther KH, Bonnema SJ, Hegedüs L. Selenium supplementation significantly reduces thyroid autoantibody levels in patients with chronic autoimmune thyroiditis: a systematic review and meta-analysis. Thyroid 2016;26(12):1681-92. PubMed
- Vinceti M, Filippini T, Rothman KJ. Selenium exposure and the risk of type 2 diabetes: a systematic review and meta-analysis. Eur J Epidemiol. 2018 Sep;33(9):789-810. Epub 2018 Jul 5. Review. PubMed
- Fallah S, Sani FV, Firoozrai M. Effect of contraceptive pill on the selenium and zinc status of healthy subjects. Contraception. 2009;80(1):40-3. PubMed
- Malpas CB, Vivash L, Genc S, et al. A Phase IIa Randomized Control Trial of VEL015 (Sodium Selenate) in Mild-Moderate Alzheimer's Disease. J Alzheimers Dis. 2016;54(1):223-232. PubMed
Alpha-lipoic Acid 48 references
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Anon. Alpha-lipoic acid. Altern Med Rev 1998;3:308-10.
- Konrad T, Vicini P, Kusterer K, et al. Alpha-lipoic acid treatment decreases serum lactate and pyruvate concentrations and improves glucose effectiveness in lean and obese patients with Type 2 diabetes. Diabetes Care 1999;22:280-7. PubMed
- Ziegler D, Hanefeld M, Ruhnau KJ, et al. Treatment of symptomatic diabetic peripheral neuropathy with the antioxidant alpha-lipoic acid: A 3-week, multicentre randomized controlled trial (ALADIN Study). Diabetologia 1995;38:1425-33.
- Gleiter CH, Schreeb KH, Freudenthaler S, et al. Lack of interaction between thioctic acid, glibenclamide and acarbose. Br J Clin Pharmacol 1999;48:819-25. PubMed
- Jacob S, Henriksen EJ, Tritschler HJ, et al. Improvement of insulin-stimulated glucose-disposal in type 2 diabetes after repeated parenteral administration of thioctic acid. Exp Clin Endocrinol Diabet 1996;104:284-8. PubMed
- Jacob S, Henriksen EJ, Schiemann AL, et al. Enhancement of glucose disposal in patients with type 2 diabetes by alpha-lipoic acid. Arzneimittelforschung 1995;45:872-4.
- Jacob S, Ruus P, Hermann R, et al. Oral administration of RAC-alpha-lipoic acid modulates insulin sensitivity in patients with type-2 diabetes mellitus: a placebo-controlled, pilot trial. Free Rad Biol Med 1999;27:309-14.
- Segermann J, Hotze A, Ulrich H, Rao GS. Effect of alpha-lipoic acid on the peripheral conversion of thyroxine to triiodothyronine and on serum lipid-, protein- and glucose levels. Arzneimittelforschung 1991;41:1294-8.
- Beitner H. Randomized, placebo controlled, double-blind study on the clinical efficacy of a cream containing 5% alpha-lipoic acid related to photoaging of facial skin. Br J Dermatol 2003;149:841-9.
- Ziegler D, Nowak H, Kempler P, et al. Treatment of symptomatic diabetic polyneuropathy with the antioxidant alpha-lipoic acid: A meta-analysis. Diabet Med 2004;21:114-21.
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Vincent HK, Bourguignon CM, Vincent KR, Taylor AG. Effects of alpha-lipoic acid supplementation in peripheral arterial disease: a pilot study. J Alt Complement Med 2007;13:577-84. PubMed
- Furukawa N, Miyamura N, Nishida K, et al. Possible relevance of alpha lipoic acid contained in a health supplement in a case of insulin autoimmune syndrome. Diabetes Res Clin Pract 2007;75:366-7. PubMed
- Ziegler D., Ametov A., Barinov A., Dyck P. J., Gurieva I., Low P. A., Munzel U., Yakhno N., Raz I., Novosadova M., Maus J., Samigullin, R. Oral treatment with alpha-lipoic acid improves symptomatic diabetic polyneuropathy: the SYDNEY 2 trial. Diabetes Car
- Gu X. M., Zhang S. S., Wu J. C., Tang Z. Y., Lu Z. Q., Li H., Liu C., Chen L., Ning, G. [Efficacy and safety of high-dose a-lipoic acid in the treatment of diabetic polyneuropathy]. Zhonghua Yi Xue Za Zhi 2010;90(35):2473-2476.
- Porasuphatana S., Suddee S., Nartnampong A., Konsil J., Harnwong B., Santaweesuk A. Glycemic and oxidative status of patients with type 2 diabetes mellitus following oral administration of alpha-lipoic acid: a randomized double-blinded placebo-controlled
- Ansar H., Mazloom Z., Kazemi F., Hejazi N. Effect of alpha-lipoic acid on blood glucose, insulin resistance and glutathione peroxidase of type 2 diabetic patients. Saudi Med J 2011;32(6):584-588. DOI
- de Oliveira A. M., Rondó P. H., Luzia L. A., D'Abronzo F. H., Illison V. K. The effects of lipoic acid and a-tocopherol supplementation on the lipid profile and insulin sensitivity of patients with type 2 diabetes mellitus: a randomized, double-blind, pla
- Mazloom Z., Ansar H. The Effect of Alpha-Lipoic Acid on Blood Pressure in Type 2 Diabetics. Iranian Journal of Endocrinology and Metabolism 2009;11(3):245-250.
- Volchegorskii I. A., Rassokhina L. M., Koliadich M. I., Alekseev M. I. [Comparative study of alpha-lipoic acid and mexidol effects on affective status, cognitive functions and quality of life in diabetes mellitus patients]. Eksp Klin Farmakol 2011;74(11):
- Cavalcanti D. R., da Silveira F. R. Alpha lipoic acid in burning mouth syndrome--a randomized double-blind placebo-controlled trial. J Oral Pathol Med 2009;38(3):254-261. PubMed
- Koh E. H., Lee W. J., Lee S. A., Kim E. H., Cho E. H., Jeong E., Kim D. W., Kim M. S., Park J. Y., Park K. G., Lee H. J., Lee I. K., Lim S., Jang H. C., Lee K. H., Lee K. U. Effects of alpha-lipoic Acid on body weight in obese subjects. Am J Med 2011;124( PubMed
- Bergqvist-Karlsson, A., Thelin, I., and Bergendorff, O. Contact dermatitis to alpha-lipoic acid in an anti-wrinkle cream. Contact Dermatitis 2006;55(1):56-57.
- Tang, J., Wingerchuk, D. M., Crum, B. A., Rubin, D. I., and Demaerschalk, B. M. Alpha-lipoic acid may improve symptomatic diabetic polyneuropathy. Neurologist. 2007;13(3):164-167. PubMed
- Hegazy SK, Tolba OA, Mostafa TM, Eid MA, El-Afify DR. Alpha-lipoic acid improves subclinical left ventricular dysfunction in asymptomatic patients with type 1 diabetes. Rev Diabet Stud 2013;10(1):58-67. PubMed
- Huang Z, Wan X, Liu J, et al. Short-term continuous subcutaneous insulin infusion combined with insulin sensitizers rosiglitazone, metformin, or antioxidant a-lipoic acid in patients with newly diagnosed type 2 diabetes mellitus. Diabetes Technol Ther 201
- Sarezky D, Raquib AR, Dunaief JL, Kim BJ. Tolerability in the elderly population of high-dose alpha lipoic acid: a potential antioxidant therapy for the eye. Clin Ophthalmol. 2016 Sep 29;10:1899-1903. PubMed
- Boriani F, Granchi D, Roatti G, Merlini L, Sabattini T, Baldini N. Alpha-lipoic acid after median nerve decompression at the carpal tunnel: a randomized controlled trial. J Hand Surg Am. 2017 Apr;42(4):236-42. PubMed
- Karkabounas S, Papadopoulos N, Anastasiadou C, et al. Effects of a-lipoic Acid, carnosine, and thiamine supplementation in obese patients with type 2 diabetes mellitus: A randomized, double-blind study. J Med Food. 2018;21(12):1197-1203.
- Murray GL, Colombo J. (r)Alpha lipoic acid is a safe, effective pharmacologic therapy of chronic orthostatic hypotension associated with low sympathetic tone. Int J Angiol. 2019;28(3):188-193. PubMed
- Bobe G, Michels AJ, Zhang WJ, et al. A randomized controlled trial of long-term (R)-α-lipoic acid supplementation promotes weight loss in overweight or obese adults without altering baseline elevated plasma triglyceride concentrations. J Nutr. 2020:
- Passiatore M, Perna A, De-Vitis R, Taccardo G. The use of alfa-lipoic acid-R (ALA-R) in patients with mild-moderate carpal tunnel syndrome: A randomised controlled open label prospective study. Malays Orthop J. 2020;14(1):1-6. PubMed
- El-Nahas MR, Elkannishy G, Abdelhafez H, Elkhamisy ET, El-Sehrawy AA. Oral alpha lipoic acid treatment for symptomatic diabetic peripheral neuropathy: A randomized double-blinded placebo-controlled study. Endocr Metab Immune Disord Drug Targets. 2020. PubMed
- Kim BJ, Hunter A, Brucker AJ, et al. Orally administered alpha lipoic acid as a treatment for geographic atrophy: A randomized clinical trial. Ophthalmol Retina. 2020;4(9):889-898. PubMed
- Derosa G, D'Angelo A, Preti P, Maffioli P. Safety and efficacy of alpha lipoic acid during 4 years of observation: A retrospective, clinical trial in healthy subjects in primary prevention. Drug Des Devel Ther. 2020;14:5367-5374.
- Sun Y, Guan X, Wang H, et al. Randomized clinical trial of combined therapy with oral a-lipoic acid and NB-UVB for nonsegmental stable vitiligo. Dermatol Ther. 2021;34(1):e14610.
- Gilron I, Robb S, Tu D, et al. Double-blind, randomized, placebo-controlled crossover trial of alpha-lipoic acid for the treatment of fibromyalgia pain: the IMPALA trial. Pain. 2021;162(2):561-568. PubMed
- Gullo D, Evans JL, Sortino G, Goldfine ID, Vigneri R. Insulin autoimmune syndrome (Hirata Disease) in European Caucasians taking a-lipoic acid. Clin Endocrinol (Oxf). 2014;81(2):204-9.
- Yukina M, Nuralieva N, Solovyev M, Troshina E, Vasilyev E. Insulin autoimmune syndrome. Endocrinol Diabetes Metab Case Rep. 2020;2020:19-0159. PubMed
- Moffa S, Improta I, Rocchetti S, Mezza T, Giaccari A. Potential cause-effect relationship between insulin autoimmune syndrome and alpha lipoic acid: Two case reports. Nutrition. 2019;57:1-4. PubMed
- Izzo V, Greco C, Corradini D, et al. Insulin autoimmune syndrome in an Argentine woman taking a-lipoic acid: A case report and review of the literature. SAGE Open Med Case Rep. 2018;6:2050313X18819601.
- EFSA Panel on Nutrition, Novel Foods and Food Allergens (NDA), Turck D, et al. Scientific opinion on the relationship between intake of alpha-lipoic acid (thioctic acid) and the risk of insulin autoimmune syndrome. EFSA J 2021;19(6):e06577. PubMed
- Jibril AT, Jayedi A, Shab-Bidar S. Efficacy and safety of oral alpha-lipoic acid supplementation for type 2 diabetes management: a systematic review and dose-response meta-analysis of randomized trials. Endocr Connect 2022;11(10):e220322. PubMed
- Corazza M, Arlotti E, Schettini N, Pacetti L, Bianchi A, Borghi A. Allergic contact dermatitis due to a-lipoic acid in a topical over-the-counter product: A case report. Contact Dermatitis 2023.
- Velasco-Amador JP, Prados-Carmona Á, Navarro-Triviño FJ. Contact urticaria syndrome caused by alpha-lipoic acid in a master formula for vulvar lichen sclerosus. Contact Dermatitis 2023;89(2):136-137. PubMed
- Sehgal T, Ohri U, Mittal N, Attri P, Dishant F. A Case of Insulin Autoimmune Syndrome in an Indian Male Taking Alpha-Lipoic Acid. Cureus 2023;15(8):e43743. PubMed
N-acetyl Cysteine (nac) 86 references
- Ellenhorn MJ, et al. Ellenhorn's Medical Toxicology: Diagnoses and Treatment of Human Poisoning. 2nd ed. Baltimore, MD: Williams & Wilkins, 1997.
- Jepsen S, Hansen AB. The influence of N-acetylcysteine on the measurement of prothrombin time and activated partial thromboplastin time in healthy subjects. Scand J Clin Lab Invest 1994;54:543-7. PubMed
- van Zandwijk N, Dalesio O, Pastorino U, et al. EUROSCAN, a randomized trial of vitamin A and N-acetylcysteine in patients with head and neck cancer or lung cancer. For the European Organization for Research and Treatment of Cancer Head and Neck and Lung C DOI
- Horowitz RS, Dart RC, Jarvie DR, et al. Placental transfer of N-acetylcysteine following human maternal acetaminophen toxicity. J Toxicol Clin Toxicol 1997;35:447-51.
- Bailey B, McGuigan MA. Management of anaphylactoid reactions to intravenous N-acetylcysteine. Ann Emerg Med 1998;31:710-5. PubMed
- Spiller HA, Krenzelok EP, Grande GA, et al. A prospective evaluation of the effect of activated charcoal before oral N-acetylcysteine in acetaminophen overdose. Ann Emerg Med 1994;23:519-23. PubMed
- Ardissino D, Merlini PA, Savonitto S, et al. Effect of transdermal nitroglycerin or N-acetylcysteine, or both, in the long-term treatment of unstable angina pectoris. J Am Coll Cardiol 1997;29:941-7. PubMed
- Horowitz JD, Henry CA, Syrjanen ML, et al. Nitroglycerine/N-acetylcysteine in the management of unstable angina pectoris. Eur Heart J 1988;9:95-100. PubMed
- Louwerse ES, Weverling GJ, Bossuyt PM, et al. Randomized, double-blind, controlled trial of acetylcysteine in amyotrophic lateral sclerosis. Arch Neurol 1995;52:559-64. PubMed
- Wiklund O, Fager G, Andersson A, et al. N-acetylcysteine treatment lowers plasma homocysteine but not serum lipoprotein(a) levels. Atherosclerosis 1996;119:99-106. PubMed
- De Flora S, Grassi C, Carati L. Attenuation of influenza-like symptomatology and improvement of cell-mediated immunity with long-term N-acetylcysteine treatment. Eur Respir J 1997;10:1535-41. PubMed
- Iversen HK. N-acetylcysteine enhances nitroglycerin-induced headache and cranial arterial responses. Clin Pharmacol Ther 1992;52:125-33. PubMed
- Behr J, Maier K, Degenkolb B, et al. Antioxidative and clinical effects of high-dose N-acetylcysteine in fibrosing alveolitis. Adjunctive therapy to maintenance immunosuppression. Am J Respir Crit Care Med 1997;156:1897-901.
- Tenenbein PK, Sitar DS, Tenenbein M. Interaction between N-acetylcysteine and activated charcoal: implications for the treatment of acetaminophen poisoning. Pharmacotherapy 2001;21:1331-6.
- Arstall MA, Yang J, Stafford I, et al. N-acetylcysteine in combination with nitroglycerin and streptokinase for the treatment of evolving acute myocardial infarction. Safety and biochemical effects. Circulation 1995;92:2855-62.
- Estensen RD, Levy M, Klopp SJ, et al. N-acetylcysteine suppression of the proliferative index in the colon of patients with previous adenomatous colonic polyps. Cancer Lett 1999;147:109-14. PubMed
- Pela R, Calcagni AM, Subiaco S, et al. N-acetylcysteine reduces the exacerbation rate in patients with moderate to severe COPD. Respiration 1999;66:495-500.. PubMed
- Oldemeyer JB, Biddle WP, Wurdeman RL, et al. Acetylcysteine in the prevention of contrast-induced nephropathy after coronary angiography. Am Heart J 2003;146:E23. . PubMed
- Ekins BR, Ford DC, Thompson MI, et al. The effect of activated charcoal on N-acetylcysteine absorption in normal subjects. Am J Emerg Med. 1987;5(6):483-7. PubMed
- Chamberlain JM, Gorman RL, Oderda GM, Klein-Schwartz W, Klein BL. Use of activated charcoal in a simulated poisoning with acetaminophen: a new loading dose for N-acetylcysteine? Ann Emerg Med. 1993;22(9):1398-402. PubMed
- Renzi FP, Donovan JW, Martin TG, Morgan L, Harrison EF. Concomitant use of activated charcoal and N-acetylcysteine. Ann Emerg Med. 1985;14(6):568-72. DOI
- North DS, Peterson RG, Krenzelok EP. Effect of activated charcoal administration on acetylcysteine serum levels in humans. Am J Hosp Pharm. 1981;38(7):1022-4. DOI
- Loscalzo J. N-Acetylcysteine potentiates inhibition of platelet aggregation by nitroglycerin. J Clin Invest. 1985;76(2):703-8. PubMed
- Ruiz FJ, Salom MG, Inglés AC, et al. N-acetyl-L-cysteine potentiates depressor response to captopril and enalaprilat in SHRs. Am J Physiol. 1994;267(3 Pt 2):R767-72. PubMed
- Deharo E, Barkan D, Krugliak M, Golenser J, Ginsburg H. Potentiation of the antimalarial action of chloroquine in rodent malaria by drugs known to reduce cellular glutathione levels. Biochem Pharmacol. 2003;66(5):809-17. PubMed
- Buckley, N. A., Whyte, I. M., O'Connell, D. L., and Dawson, A. H. Oral or intravenous N-acetylcysteine: which is the treatment of choice for acetaminophen (paracetamol) poisoning? J Toxicol.Clin Toxicol. 1999;37(6):759-767.
- Sunman, W., Hughes, A. D., and Sever, P. S. Anaphylactoid response to intravenous acetylcysteine. Lancet 5-16-1992;339(8803):1231-1232. PubMed
- Reynard, K., Riley, A., and Walker, B. E. Respiratory arrest after N-acetylcysteine for paracetamol overdose. Lancet 9-12-1992;340(8820):675. PubMed
- BERNSTEIN, I. L. and AUSDENMOORE, R. W. IATROGENIC BRONCHOSPASM OCCURRING DURING CLINICAL TRIALS OF A NEW MUCOLYTIC AGENT, ACETYLCYSTEINE. Dis.Chest 1964;46:469-473. PubMed
- REAS, H. W. THE USE OF N-ACETYLCYSTEINE IN THE TREATMENT OF CYSTIC FIBROSIS. J Pediatr 1964;65:542-557. PubMed
- Bibi, H., Seifert, B., Oullette, M., and Belik, J. Intratracheal N-acetylcysteine use in infants with chronic lung disease. Acta Paediatr. 1992;81(4):335-339. PubMed
- Jepsen, S., Herlevsen, P., Knudsen, P., Bud, M. I., and Klausen, N. O. Antioxidant treatment with N-acetylcysteine during adult respiratory distress syndrome: a prospective, randomized, placebo-controlled study. Crit Care Med 1992;20(7):918-923. PubMed
- Roes, E. M., Raijmakers, M. T., Boo, T. M., Zusterzeel, P. L., Merkus, H. M., Peters, W. H., and Steegers, E. A. Oral N-acetylcysteine administration does not stabilise the process of established severe preeclampsia. Eur.J Obstet.Gynecol.Reprod.Biol 2006
- Spiller, H. A., Winter, M. L., Klein-Schwartz, W., and Bangh, S. A. Efficacy of activated charcoal administered more than four hours after acetaminophen overdose. J Emerg.Med 2006;30(1):1-5. PubMed
- Tirouvanziam, R., Conrad, C. K., Bottiglieri, T., Herzenberg, L. A., Moss, R. B., and Herzenberg, L. A. High-dose oral N-acetylcysteine, a glutathione prodrug, modulates inflammation in cystic fibrosis. Proc Natl.Acad.Sci U.S.A 3-21-2006;103(12):4628-463
- Niemi, T. T., Munsterhjelm, E., Poyhia, R., Hynninen, M. S., and Salmenpera, M. T. The effect of N-acetylcysteine on blood coagulation and platelet function in patients undergoing open repair of abdominal aortic aneurysm. Blood Coagul.Fibrinolysis 2006;1 PubMed
- Komisarof, J. A., Gilkey, G. M., Peters, D. M., Koudelka, C. W., Meyer, M. M., and Smith, S. M. N-acetylcysteine for patients with prolonged hypotension as prophylaxis for acute renal failure (NEPHRON). Crit Care Med 2007;35(2):435-441. PubMed
- Grimble, G. K. Adverse gastrointestinal effects of arginine and related amino acids. J Nutr 2007;137(6 Suppl 2):1693S-1701S. PubMed
- Berk, M., Copolov, D. L., Dean, O., Lu, K., Jeavons, S., Schapkaitz, I., Anderson-Hunt, M., and Bush, A. I. N-acetyl cysteine for depressive symptoms in bipolar disorder--a double-blind randomized placebo-controlled trial. Biol Psychiatry 9-15-2008;64(6) PubMed
- Shahin, A. Y., Hassanin, I. M., Ismail, A. M., Kruessel, J. S., and Hirchenhain, J. Effect of oral N-acetyl cysteine on recurrent preterm labor following treatment for bacterial vaginosis. Int J Gynaecol.Obstet. 2009;104(1):44-48. PubMed
- Nigwekar, S. U. and Kandula, P. N-acetylcysteine in cardiovascular-surgery-associated renal failure: a meta-analysis. Ann Thorac.Surg 2009;87(1):139-147. PubMed
- Sandilands, E. A. and Bateman, D. N. Adverse reactions associated with acetylcysteine. Clin Toxicol.(Phila) 2009;47(2):81-88. PubMed
- Wijeysundera, D. N., Karkouti, K., Rao, V., Granton, J. T., Chan, C. T., Raban, R., Carroll, J., Poonawala, H., and Beattie, W. S. N-acetylcysteine is associated with increased blood loss and blood product utilization during cardiac surgery. Crit Care Me PubMed
- Holdiness, M. R. Clinical pharmacokinetics of N-acetylcysteine. Clin Pharmacokinet. 1991;20(2):123-134. PubMed
- Dawson, A. H., Henry, D. A., and McEwen, J. Adverse reactions to N-acetylcysteine during treatment for paracetamol poisoning. Med J Aust. 3-20-1989;150(6):329-331.
- Rasmussen, J. B. and Glennow, C. Reduction in days of illness after long-term treatment with N-acetylcysteine controlled-release tablets in patients with chronic bronchitis. Eur.Respir.J 1988;1(4):351-355. DOI
- Walters, M. T., Rubin, C. E., Keightley, S. J., Ward, C. D., and Cawley, M. I. A double-blind, cross-over, study of oral N-acetylcysteine in Sjogren's syndrome. Scand J Rheumatol.Suppl 1986;61:253-258.
- Cato, A., Goldstein, I., and Millman, M. A double-blind parallel study of acetylcysteine-isoproterenol and saline-isoproterenol in patients with chronic obstructive lung disease. J Int Med Res 1977;5(3):175-183. PubMed
- Parr, G. D. and Huitson, A. Oral Fabrol (oral N-acetyl-cysteine) in chronic bronchitis. Br.J.Dis.Chest 1987;81(4):341-348.
- Dano, G. Bronchospasm caused by acetylcysteine in children with bronchial asthma. Acta Allergol. 1971;26(3):181-190. DOI
- Howatt, W. F. and DeMuth, G. R. A double-blind study of the use of acetylcysteine in patients with cystic fibrosis. Univ Mich.Med Cent.J 1966;32(2):82-85.
- Millman, M. and Grundon, W. Use of acetylcysteine in bronchial asthma and emphysema. J Asthma Res 1969;6(4):199-209. PubMed
- Vale, J. A. and Wheeler, D. C. Anaphylactoid reaction to acetylcysteine. Lancet 10-30-1982;2(8305):988.
- Mant, T. G., Tempowski, J. H., Volans, G. N., and Talbot, J. C. Adverse reactions to acetylcysteine and effects of overdose. Br Med J (Clin Res Ed) 7-28-1984;289(6439):217-219. PubMed
- Myers, C., Bonow, R., Palmeri, S., Jenkins, J., Corden, B., Locker, G., Doroshow, J., and Epstein, S. A randomized controlled trial assessing the prevention of doxorubicin cardiomyopathy by N-acetylcysteine. Semin.Oncol 1983;10(1 Suppl 1):53-55.
- Miller, L. F. and Rumack, B. H. Clinical safety of high oral doses of acetylcysteine. Semin.Oncol 1983;10(1 Suppl 1):76-85.
- Boman, G., Backer, U., Larsson, S., Melander, B., and Wahlander, L. Oral acetylcysteine reduces exacerbation rate in chronic bronchitis: report of a trial organized by the Swedish Society for Pulmonary Diseases. Eur J Respir.Dis 1983;64(6):405-415.
- Tattersall, A. B., Bridgman, K. M., and Huitson, A. Irish general practice study of acetylcysteine (Fabrol) in chronic bronchitis. J Int Med Res 1984;12(2):96-101. PubMed
- Jackson, I. M., Barnes, J., and Cooksey, P. Efficacy and tolerability of oral acetylcysteine (Fabrol) in chronic bronchitis: a double-blind placebo controlled study. J Int Med Res 1984;12(3):198-206. PubMed
- Ho, S. W. and Beilin, L. J. Asthma associated with N-acetylcysteine infusion and paracetamol poisoning: report of two cases. Br Med J (Clin Res Ed) 9-24-1983;287(6396):876-877. PubMed
- Vale, J. A. and Buckley, B. M. Asthma associated with N-acetylcysteine infusion and paracetamol poisoning. Br Med J (Clin Res Ed) 10-22-1983;287(6400):1223. PubMed
- Bateman, D. N., Woodhouse, K. W., and Rawlins, M. D. Adverse reactions to N-acetylcysteine. Hum Toxicol. 1984;3(5):393-398. PubMed
- Gervais, S., Lussier-Labelle, F., and Beaudet, G. Anaphylactoid reaction to acetylcysteine. Clin Pharm 1984;3(6):586-587.
- Tattersall, A. B., Bridgman, K. M., and Huitson, A. Acetylcysteine (Fabrol) in chronic bronchitis--a study in general practice. J Int Med Res 1983;11(5):279-284. PubMed
- Casola, G. and vanSonnenberg, E. Skin damage from acetylcysteine leak during percutaneous abscess drainage. Radiology 1984;152(1):233. PubMed
- Aylward, M., Maddock, J., and Dewland, P. Clinical evaluation of acetylcysteine in the treatment of patients with chronic obstructive bronchitis: a balanced double-blind trial with placebo control. Eur.J Respir.Dis.Suppl 1980;111:81-89.
- Long-term oral acetylcysteine in chronic bronchitis. a double-blind controlled study. Eur.J Respir.Dis.Suppl 1980;111:93-108.
- Chan, T. Y. and Critchley, J. A. Adverse reactions to intravenous N-acetylcysteine in Chinese patients with paracetamol (acetaminophen) poisoning. Hum Exp.Toxicol. 1994;13(8):542-544. PubMed
- Hansen, N. C., Skriver, A., Brorsen-Riis, L., Balslov, S., Evald, T., Maltbaek, N., Gunnersen, G., Garsdal, P., Sander, P., Pedersen, J. Z., and . Orally administered N-acetylcysteine may improve general well-being in patients with mild chronic bronchiti
- Reid, M. B., Stokic, D. S., Koch, S. M., Khawli, F. A., and Leis, A. A. N-acetylcysteine inhibits muscle fatigue in humans. J Clin Invest 1994;94(6):2468-2474. PubMed
- Chirkov, Y. Y. and Horowitz, J. D. N-Acetylcysteine potentiates nitroglycerin-induced reversal of platelet aggregation. J Cardiovasc.Pharmacol 1996;28(3):375-380. PubMed
- Hershkovitz, E., Shorer, Z., Levitas, A., and Tal, A. Status epilepticus following intravenous N-acetylcysteine therapy. Isr.J Med Sci 1996;32(11):1102-1104.
- Stavem, K. [Anaphylactic reaction to N-acetylcysteine after poisoning with paracetamol]. Tidsskr.Nor Laegeforen. 5-30-1997;117(14):2038-2039.
- Walton, N. G., Mann, T. A., and Shaw, K. M. Anaphylactoid reaction to N-acetylcysteine. Lancet 12-15-1979;2(8155):1298. PubMed
- Perry, H. E. and Shannon, M. W. Efficacy of oral versus intravenous N-acetylcysteine in acetaminophen overdose: results of an open-label, clinical trial. J Pediatr 1998;132(1):149-152. PubMed
- Kory, R. C., Hirsch, S. R., and Giraldo, J. Nebulization of N-acetylcysteine combined with a bronchodilator in patients with chronic bronchitis. A controlled study. Chest 1968;54(6):504-509. PubMed
- Nahir, A. M., Scharf, J. M., and Szargel, R. Effects of oral N-acetylcysteine on both ocular and oral manifestations of Sjogren's Syndrome. Curr Ther Res 1989;46:187-192.
- Charley, G., Dean, B. S., and Krenzelok, E. P. Oral N-acetylcysteine-induced urticaria: a case report. Vet.Hum Toxicol. 1987;29:477.
- Jenkins DD, Wiest DB, Mulvihill DM, et al. Fetal and neonatal effects of N-acetylcysteine when used for neuroprotection in maternal chorioamnionitis. J Pediatr. 2016 Jan;168:67-76.e6. PubMed
- Costa DLC, Diniz JB, Requena G, et al. Randomized double-blind, placebo-controlled trial of N-acetylcysteine augmentation for treatment-resistant obsessive-compulsive disorder. J Clin Psychiatry. 2017 Jul;78(7):e799-e773.
- Kranzer K, Elamin WF, Cox H, Seddon JA, Ford N, Drobniewski F. A systematic review and meta-analysis of the efficacy and safety of N-acetylcysteine in preventing aminoglycoside-induced ototoxicity: implications for the treatment of multidrug-resistant TB.
- Wang W, Zhang Y, Liu Y, Xu L, Shi D. Severe chest pain due to N-acetylcysteine-induced esophagitis. Case Rep Med. 2019;2019:8057259.
- Li F, Welling MC, Johnson JA, et al. N-acetylcysteine for pediatric obsessive-compulsive disorder: A small pilot study. J Child Adolesc Psychopharmacol. 2020;30(1):32-37. PubMed
- Monti DA, Zabrecky G, Leist TP, et al. N-acetyl cysteine administration is associated with increased cerebral glucose metabolism in patients with multiple sclerosis: An exploratory study. Front Neurol. 2020;11:88. PubMed
- Gray KM, Carpenter MJ, Baker NL, et al. A double-blind randomized controlled trial of N-acetylcysteine in cannabis-dependent adolescents. Am J Psychiatry. 2012;169(8):805-12.
- Sarris J, Byrne G, Castle D, et al. N-acetyl cysteine (NAC) augmentation in the treatment of obsessive-compulsive disorder: A phase III, 20-week, double-blind, randomized, placebo-controlled trial. Prog Neuropsychopharmacol Biol Psychiatry 2022;117:110550 PubMed
See these in context on the N-acetyl Cysteine (nac) monograph →
Milk Thistle 69 references
- Ferenci P, Dragosics B, Dittrich H, et al. Randomized controlled trial of silymarin treatment in patients with cirrhosis of the liver. J Hepatol 1989;9:105-13. PubMed
- Anon. Milk thistle: Effects on liver disease and cirrhosis and clinical adverse effects. Summary, Evidence Report/Technology Assessment: Number 21, September 2000. Agency for Healthcare Research and Quality, Rockville, MD. Available at: http://www.ahrq.g
- Beckmann-Knopp S, Rietbrock S, Weyhenmeyer R, et al. Inhibitory effects of silibinin on cytochrome P-450 enzymes in human liver microsomes. Pharmacol Toxicol 2000;86:250-6. PubMed
- Venkataramanan R, Ramachandran V, Komoroski BJ, et al. Milk thistle, a herbal supplement, decreases the activity of CYP3A4 and uridine diphosphoglucuronosyl transferase in human hepatocyte cultures. Drug Metab Dispos 2000;28:1270-3. DOI
- Kim DH, Jin YH, Park JB, Kobashi K. Silymarin and its components are inhibitors of beta-glucuronidase. Biol Pharm Bull 1994;17:443-5. PubMed
- Pares A, Planas R, Torres M, et al. Effects of silymarin in alcoholic patients with cirrhosis of the liver: results of a controlled, double-blind, randomized and multicenter trial. J Hepatol 1998;28:615-21. PubMed
- Piscitelli SC, Formentini E, Burstein AH, et al. Effect of milk thistle on the pharmacokinetics of indinavir in healthy volunteers. Pharmacotherapy 2002;22:551-6. PubMed
- Boerth J, Strong KM. The clinical utility of milk thistle (Silybum marianum) in cirrhosis of the liver. J Herb Pharmacother 2002;2:11-7.
- Tanamly MD, Tadros F, Labeeb S, et al. Randomised double-blinded trial evaluating silymarin for chronic hepatitis C in an Egyptian village: study description and 12-month results. Dig Liver Dis 2004;36:752-9. PubMed
- Gurley BJ, Gardner SF, Hubbard MA, et al. In vivo assessment of botanical supplementation on human cytochrome P450 phenotypes: Citrus aurantium, Echinacea purpurea, milk thistle, and saw palmetto. Clin Pharmacol Ther 2004;76:428-40. .
- Huseini HF, Larijani B, Heshmat R, et al. The efficacy of Silybum marianum (L.) Gaertn. (silymarin) in the treatment of type II diabetes: a randomized, double-blind, placebo-controlled, clinical trial. Phytother Res 2006;20;1036-9.
- Deng JW, Shon JH, Shin HJ, et al. Effect of silymarin supplement on the pharmacokinetics of rosuvastatin. Pharm Res 2008;25:1807-14. PubMed
- Kim CS, Choi SJ, Park CY, et al. Effects of silybinin on the pharmacokinetics of tamoxifen and its active metabolite, 4-hydroxytamoxifen in rats. Anticancer Res 2010;30:79-85.
- Sridar C, Goosen TC, Kent UM, et al. Silybin inactivates cytochromes P450 3A4 and 2C9 and inhibits major hepatic glucuronosyltransferases. Drug Metab Dispos 2004;32:587-94. PubMed
- van Erp NP, Baker SD, Zhao M, et al. Effect of milk thistle (Silybum marianum) on the pharmacokinetics of irinotecan. Clin Cancer Res 2005;11:7800-6.
- Budzinski JW, Trudeau VL, Drouin CE, et al. Modulation of human cytochrome P450 3A4 (CYP3A4) and P-glycoprotein (P-gp) in Caco-2 cell monolayers by selected commercial-source milk thistle and goldenseal products. Can J Physiol Pharmacol 2007;85:966-78.
- Doehmer J, Weiss G, McGregor GP, Appel K. Assessment of a dry extract from milk thistle (Silybum marianum) for interference with human liver cytochrome-P450 activities. Toxicol In Vitro 2011;25:21-7. PubMed
- Jiao Z, Shi XJ, Li ZD, et al. Population pharmacokinetics of sirolimus in de novo Chinese adult renal transplant patients. Br.J.Clin.Pharmacol. 2009;68(1):47-60.
- Gurley, B. J., Barone, G. W., Williams, D. K., Carrier, J., Breen, P., Yates, C. R., Song, P. F., Hubbard, M. A., Tong, Y., and Cheboyina, S. Effect of milk thistle (Silybum marianum) and black cohosh (Cimicifuga racemosa) supplementation on digoxin phar
- Allain, H., Schuck, S., Lebreton, S., Strenge-Hesse, A., Braun, W., Gandon, J. M., and Brissot, P. Aminotransferase levels and silymarin in de novo tacrine-treated patients with Alzheimer's disease. Dement.Geriatr.Cogn Disord. 1999;10(3):181-185. PubMed
- Angulo, P., Patel, T., Jorgensen, R. A., Therneau, T. M., and Lindor, K. D. Silymarin in the treatment of patients with primary biliary cirrhosis with a suboptimal response to ursodeoxycholic acid. Hepatology 2000;32(5):897-900. PubMed
- Bean, P. The use of alternative medicine in the treatment of hepatitis C. Am.Clin.Lab 2002;21(4):19-21.
- Hussain, S. A. Silymarin as an adjunct to glibenclamide therapy improves long-term and postprandial glycemic control and body mass index in type 2 diabetes. J.Med.Food 2007;10(3):543-547. PubMed
- El-Kamary, S. S., Shardell, M. D., Abdel-Hamid, M., Ismail, S., El-Ateek, M., Metwally, M., Mikhail, N., Hashem, M., Mousa, A., Aboul-Fotouh, A., El-Kassas, M., Esmat, G., and Strickland, G. T. A randomized controlled trial to assess the safety and effic
- Gharagozloo, M., Moayedi, B., Zakerinia, M., Hamidi, M., Karimi, M., Maracy, M., and Amirghofran, Z. Combined therapy of silymarin and desferrioxamine in patients with beta-thalassemia major: a randomized double-blind clinical trial. Fundam.Clin.Pharmaco
- Ladas, E. J., Kroll, D. J., Oberlies, N. H., Cheng, B., Ndao, D. H., Rheingold, S. R., and Kelly, K. M. A randomized, controlled, double-blind, pilot study of milk thistle for the treatment of hepatotoxicity in childhood acute lymphoblastic leukemia (ALL PubMed
- Sayyah, M., Boostani, H., Pakseresht, S., and Malayeri, A. Comparison of Silybum marianum (L.) Gaertn. with fluoxetine in the treatment of Obsessive-Compulsive Disorder. Prog.Neuropsychopharmacol.Biol.Psychiatry 3-17-2010;34(2):362-365. PubMed
- Flaig, T. W., Glode, M., Gustafson, D., van, Bokhoven A., Tao, Y., Wilson, S., Su, L. J., Li, Y., Harrison, G., Agarwal, R., Crawford, E. D., Lucia, M. S., and Pollak, M. A study of high-dose oral silybin-phytosome followed by prostatectomy in patients w
- Ramirez-Santos, A., Perez-Bustillo, A., Gonzalez-Sixto, B., Suarez-Amor, O., and Rodriguez-Prieto, M. A. [Acute generalized exanthematous pustulosis due to milk thistle (Silybum marianum) tea]. Actas Dermosifiliogr. 2011;102(9):744-745. DOI
- Loguercio C, Andreone P, Brisc C, et al. Silybin combined with phosphatidylcholine and vitamin E in patients with nonalcoholic fatty liver disease: a randomized controlled trial. Free Radic Biol Med 2012;52(9):1658-65. PubMed
- Yakoot, M. and Salem, A. Spirulina platensis versus silymarin in the treatment of chronic hepatitis C virus infection. A pilot randomized, comparative clinical trial. BMC.Gastroenterol. 2012;12:32. PubMed
- Fallahzadeh, M. K., Dormanesh, B., Sagheb, M. M., Roozbeh, J., Vessal, G., Pakfetrat, M., Daneshbod, Y., Kamali-Sarvestani, E., and Lankarani, K. B. Effect of addition of silymarin to renin-angiotensin system inhibitors on proteinuria in type 2 diabetic
- Fried, M. W., Navarro, V. J., Afdhal, N., Belle, S. H., Wahed, A. S., Hawke, R. L., Doo, E., Meyers, C. M., and Reddy, K. R. Effect of silymarin (milk thistle) on liver disease in patients with chronic hepatitis C unsuccessfully treated with interferon t
- Fallah Huseini, H., Larijani, B., Fakhrzadeh, H., Rajabi Pour, B., Akhondzadeh, S., Toliat, T., and Heshmat, R. The clinical trial of Silybum Marianum seed extract (Silymarin) on type II diabetic patients with hyperlipidemia. Iran J.Diabetes Lipid Disord
- Mironets VI, Krasovskaia EA, and Polishchuk II. [A case of urticaria during Carsil treatment]. Vrach Delo 1990;7:86-87.
- Velussi M, Cernigoi AM, Viezzoli L, and et al. Silymarin reduces hyperinsulinemia, malondialdehyde levels, and daily insulin need in cirrhotic diabetic patients. Curr Ther Res 1993;53(5):533-545. DOI
- Marcelli R, Bizzoni P, Conte D, and et al. Randomized controlled study of the efficacy and tolerability of a short course of IdB 1016 in the treatment of chronic persistent hepatitis. Eur Bull Drug Res 1992;1(3):131-135.
- Vailati A, Aristia L, Sozze E, and et al. Randomized open study of the dose-effect relationship of a short course of IdB 1016 in patients with viral or alcoholic hepatitis. Fitoterapia 1993;64(3):219-228.
- Marena C and Lampertico M. Preliminary clinical development of silipide: a new complex of silybin in toxic liver disorders. Planta Med 1991;57(2):A124-A125. DOI
- Grungreiff K, Albrecht M, and Strenge-Hesse A. Benefit of medicinal liver therapy in general practice. Med Welt 1995;46:222-227.
- Frerick F, Kuhn U, and Strenge-Hesse A. Silymarin--ein Phytopharmakon zur Behandlung toxischen Leberschaden: Anwendungsbeobachtung bei 2169 Patienten. Kassenarzt 1990;33:36-41.
- Schuppan D, Strosser W, Burkard G, and et al. Influence of Legalon(TM) 140 on the metabolism of collagen in patients with chronic liver disease--Review by measurement of PIIINP-values. Zeitschrift fur Allgemeinmedizin 1998;74:577-584.
- Studlar M. Die Behandlung chronischer Leberkrankungen mit Silymarin und B-Vitaminen. Therapiewoche 1985;35:3375-3378.
- Anon. Adverse reaction: milk thistle-associated toxicity. Nurse Drug Alert 1999;23(7):51.
- Gufford BT, Chen G, Vergara AG, et al. Milk Thistle Constituents Inhibit Raloxifene Intestinal Glucuronidation: A Potential Clinically Relevant Natural Product-Drug Interaction. Drug Metab Dispos. 2015;43(9):1353-9. PubMed
- El-Shitany NA, Hegazy S, El-Desoky K. Evidences for antiosteoporotic and selective estrogen receptor modulator activity of silymarin compared with ethinylestradiol in ovariectomized rats. Phytomedicine. 2010;17(2):116-25. PubMed
- Seidlová-Wuttke D, Becker T, Christoffel V, Jarry H, Wuttke W. Silymarin is a selective estrogen receptor beta (ERbeta) agonist and has estrogenic effects in the metaphysis of the femur but no or antiestrogenic effects in the uterus of ovariectomized (ovx
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Derosa G, Romano D, D'Angelo A, Maffioli P. Berberis aristata/Silybum marianum fixed combination (Berberol(®)) effects on lipid profile in dyslipidemic patients intolerant to statins at high dosages: a randomized, placebo-controlled, clinical trial. Phyto PubMed
- Luangchosiri C, Thakkinstian A, Chitphuk S, Stitchantrakul W, Petraksa S, Sobhonslidsuk A. A double-blinded randomized controlled trial of silymarin for the prevention of antituberculosis drug-induced liver injury. BMC Complement Altern Med. 2015;15:334. PubMed
- Kawaguchi-Suzuki M, Frye RF, Zhu HJ, et al. The effects of milk thistle (Silybum marianum) on human cytochrome P450 activity. Drug Metab Dispos. 2014;42(10):1611-6. PubMed
- Rastegarpanah M, Malekzadeh R, Vahedi H, et al. A randomized, double blinded, placebo-controlled clinical trial of silymarin in ulcerative colitis. Chin J Integr Med. 2015;21(12):902-6. PubMed
- Di Pierro F, Bellone I, Rapacioli G, Putignano P. Clinical role of a fixed combination of standardized Berberis aristata and Silybum marianum extracts in diabetic and hypercholesterolemic patients intolerant to statins. Diabetes Metab Syndr Obes. 2015;8:8 PubMed
- Di Pierro F, Villanova N, Agostini F, Marzocchi R, Soverini V, Marchesini G. Pilot study on the additive effects of berberine and oral type 2 diabetes agents for patients with suboptimal glycemic control. Diabetes Metab Syndr Obes. 2012;5:213-7. PubMed
- Guarino G, Strollo F, Carbone L, et al. Bioimpedance analysis, metabolic effects and safety of the association Berberis aristata/Bilybum marianum: a 52-week double-blind, placebo-controlled study in obese patients with type 2 diabetes. J Biol Regul Homeos
- Ebrahimpour-Koujan S, Gargari BP, Mobasseri M, Valizadeh H, Asghari-Jafarabadi M. Lower glycemic indices and lipid profile among type 2 diabetes mellitus patients who received novel dose of Silybum marianum (L.) Gaertn. (silymarin) extract supplement: A T
- Lash DB, Ward S. CYP2C9-mediated warfarin and milk thistle interaction. J Clin Pharm Ther. 2019. PubMed
- Malekshah RE, Khaleghian A. Influence of Silybum marianum on morphine addicted rats, biochemical parameters and molecular simulation studies on µ-opioid receptor. Drug Res (Stuttg). 2019;69(11):630-638. PubMed
- Soleymani S, Ayati MH, Mansourzadeh MJ, Namazi N, Zargaran A. The effects of Silymarin on the features of cardiometabolic syndrome in adults: A systematic review and meta-analysis. Phytother Res. 2022 Jan 11. doi: 10.1002/ptr.7364. PubMed
- Gamissans M, Expósito-Serrano V, López-Llunell C, Valdivieso L, Garbayo-Salmons P. Bullous pemphigoid triggered by Silybum marianum: an unexpected side effect of an herbal remedy. Int J Dermatol. 2021 Aug 7. doi: 10.1111/ijd.15822. PubMed
- Aboras SI, Korany MA, El-Yazbi AF, Ragab MAA, Abdine HH. In-depth investigation of the Silymarin effect on the pharmacokinetic parameters of sofosbuvir, GS-331007 and ledipasvir in rat plasma using LC-MS. Biomed Chromatogr 2022;36(9):e5427. PubMed
- Wattanakrai P, Nimmannitya K. A Randomized, Double-Blind, Split-Face Study of Topical Silymarin vs 2% Hydroquinone Cream in Melasmas. J Drugs Dermatol 2022;21(12):1304-1310. PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
- Zhang W, Zhang Y, Wen C, Jiang X, Wang L. In vitro Assessment of the Effects of Silybin on CYP2B6-mediated Metabolism. Planta Med 2023. PubMed
- Bechtold BJ, Lynch KD, Oyanna VO, et al. Rifampin- and Silymarin-Mediated Pharmacokinetic Interactions of Exogenous and Endogenous Substrates in a Transgenic OATP1B Mouse Model. Mol Pharm 2024;21(5):2284-2297. PubMed
- Mohammadi S, Asbaghi O, Afrisham R, et al. Impacts of Supplementation with Silymarin on Cardiovascular Risk Factors: A Systematic Review and Dose-Response Meta-Analysis. Antioxidants (Basel) 2024;13(4):390. PubMed
- Rustamzadeh A, Sadigh N, Vahabi Z, et al. Effects silymarin and rosuvastatin on amyloid-carriers level in dyslipidemic Alzheimer's patients: A double-blind placebo-controlled randomized clinical trial. IBRO Neurosci Rep 2024;17:108-121. PubMed
- Fatemi Shandiz A, Karimi G, Dayyani M, Hosseini S, Elyasi S. Evaluation of oral silymarin formulation efficacy in prevention of doxorubicin induced hepatotoxicity in patients with non-metastatic breast cancer. J Oncol Pharm Pract 2024. PubMed
- Duan X, Bai W, Hu J, et al. Inhibitory effect of flavonoids on multidrug and toxin extrusion protein 1 function: Implications for food/herb-drug interaction and drug-induced kidney injury. J Appl Toxicol 2024;44(9):1388-1402. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC