
Corti-B Plex Ingredients & Drug Interactions
by NuMedica
What is this page for?
First and foremost: checking Corti-B Plex against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Corti-B Plex is a dietary supplement by NuMedica with 7 active ingredients. Its ingredients are commonly taken for general nutrition and energy, skin and hair health, acne (topical and oral).Based on those ingredients, 1,384 medications have a known interaction with it, the most serious rated moderate. The ingredients most likely to interact are Citrus Bioflavonoids, BioPerine, Vitamin B6. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Corti-B Plex by NuMedica
Ask about any prescription or over-the-counter medication and we check it for interactions with Corti-B Plex by NuMedica — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Corti-B Plex by NuMedica
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
Corti-B Plex contains 7 active ingredients. Pantothenic acid (a B vitamin) supports energy metabolism and is proven effective for pantothenic acid deficiency.
Folate is a B vitamin needed for DNA and cell function. BioPerine is black pepper extract, added to enhance absorption of other nutrients.
Acetyl-L-carnitine is an amino acid derivative that may support cognitive function and nerve health. Vitamin C is an antioxidant needed for immune function and collagen formation.
Vitamin B6 helps with metabolism and nerve function. Quatrefolic is a form of folate.
Two inactive ingredients—hydroxypropyl methylcellulose and bamboo silica—serve as the capsule material and flow agent.
Does it work?
Moderate evidence
Evidence for this product's overall use is not established in our data. However, individual ingredients have been studied: pantothenic acid is effective for pantothenic acid deficiency.
Acetyl-L-carnitine is possibly effective for age-related cognitive decline, Alzheimer disease, alcohol use disorder, diabetic nerve pain (neuropathy), and depression. Vitamin C is effective for vitamin C deficiency and possibly effective for anemia, heart rhythm problems, cataracts, and exercise-induced respiratory infections.
Vitamin B6 is effective for certain types of anemia, vitamin B6 deficiency, and seizure disorders; it's possibly effective for elevated homocysteine and pregnancy-related nausea and vomiting. BioPerine and Citrus Bioflavonoids do not have established effectiveness ratings in our data.
How safe is it?
Well-documented data
Most ingredients are generally well tolerated at standard doses. Pantothenic acid is considered safe at typical supplement doses.
Vitamin C is safe at normal dietary and supplement doses but can cause diarrhea, nausea, and headache at very high doses (above 2 grams daily), and people prone to kidney stones should be cautious. Acetyl-L-carnitine is generally well tolerated short-term; reported side effects include agitation, dry mouth, headache, insomnia, reduced appetite, and a fishy odor to urine and sweat.
Vitamin B6 at normal amounts is safe, but high doses over time can damage nerves. BioPerine is generally safe as a food spice but should be used cautiously in concentrated supplement form; side effects may include burning aftertaste and stomach upset.
There is not enough long-term safety data on acetyl-L-carnitine. Safety data for Quatrefolic and Citrus Bioflavonoids is not on file.
Meds to double-check
Moderate interaction found
Before taking Corti-B Plex, check with your pharmacist if you take: seizure medications (phenytoin, phenobarbital), blood thinners (warfarin, acenocoumarol), heart medications (propranolol, amiodarone), antiviral drugs (nevirapine), antibiotics (rifampin), oral contraceptives or hormone replacement therapy, blood pressure medications, thyroid hormone replacement, antidepressants or other serotonergic drugs, or chemotherapy medications. These are the main drug types documented to interact with ingredients in this product.
The bottom line
Scorecard at a glanceFully disclosed formula with some supporting evidence for its stated purpose. Moderate medication interactions have been identified, and safety information is well characterized.
This product may help with B vitamin nutrition and certain uses like cognitive support or nerve health, depending on your needs. If you take seizure medications, blood thinners, antidepressants, antiviral drugs, heart medications, or thyroid medication, check your specific drugs with the tool on this page before starting.
Talk with your pharmacist or doctor about whether this product fits your health plan.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 6 of 7 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jun 25, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Corti-B Plex, straight from the product label.
| Brand | NuMedica |
|---|---|
| Barcode (UPC) | 812527010819 |
| Net contents | 120 Vegetable Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Jun 25, 2025 |
| DSLD ID | 323506 |
| Product type | Other Combinations |
| Supplement form | Capsule |
| Dietary claims / uses | Nutrient, All Other, Structure/Function |
| Intended target group(s) | Vegetarian, Adult (18 - 50 Years), Gluten Free, Dairy Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
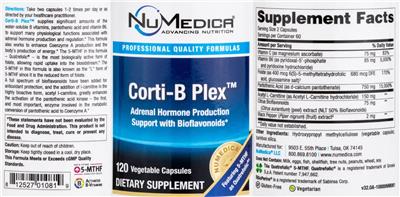
Supplement Facts
The label details for Corti-B Plex by NuMedica, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Pantothenic Acid | 750 mg | 15000% |
| Folate | 680 mcg DFE | 170% |
| BioPerine | 2 mg | -- |
| Acetyl-L-Carnitine | 150 mg | -- |
| Vitamin C | 75 mg | 83% |
| Vitamin B6 | 85 mg | 5000% |
| Quatrefolic | 400 mcg | -- |
| Citrus Bioflavonoids | 75 mg | -- |
Other ingredients: Hydroxypropyl Methylcellulose, Bamboo Silica
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Suggested/Recommended/Usage/Directions
Directions: Take two capsules 1-2 times per day or as directed by your healthcare practitioner.
Formula
Corti-B Plex supplies significant amounts of the water-soluble B vitamins, pantothenic acid and Vitamin B6, to support many physiological functions associated with adrenal hormone production and regulation. This formula also works to enhance Coenzyme A production and the body's production of energy. The 5-MTHF in this formula - Quatrefolic - is the most biologically active form of folate, allowing rapid uptake into the bloodstream. The 5-MTHF in this formula is also known as the "L" form of 5-MTHF since it is the reduced form of folate. A full spectrum of bioflavonoids have been added for antioxidant protection, and the addition of I-carnitine in the highly bioactive form, acetyl I-carnitine, greatly enhances the activation of the pantothenic acid kinase - the first, and most important, enzyme involved in the metabolic conversion of pantothenic acid to Coenzyme A.
Rapid Uptake 5-MTHF Bioactive Folate B Activated B-Vitamins
Corti-B Plex Featuring 5-MTHF as Quatrefolic
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure or prevent any disease.
Precautions
Caution: Keep out of reach of children.
Storage
Storage: Keep tightly closed in a cool, dry place.
Formulation
This formula meets or exceeds cGMP Quality Standards.
Professional quality formulas Adrenal hormone production support with Bioflavonoids
Does not contain: Milk, eggs, fish, shellfish, tree nuts, peanuts, wheat, soy.
GF Gluten-free
Vegetarian
Brand IP Statement(s)
NuMedica Advancing Nutrition
Quatrefolic is a registered trademark of Gnosis S.p.A. Patent number 7,947,662. BioPerine is a registered trademark of Sabinsa Corp.
FDA Statement of Identity
Dietary Supplement
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Corti-B Plex by NuMedica label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Corti-B Plex by NuMedica
These are the 7 active ingredients this product is made of. Select any to open its full monograph.
Serving size2 Capsule(s) Dosage formCapsule Servings per container60 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Pantothenic Acid
No knowninteractions
Pantothenic acid is vitamin B5, an essential nutrient your body uses to turn food into energy. True deficiency is very rare because it is found in nea...
Pantothenic Acid monograph & interactionsFolate
- › Quatrefolic
BioPerine
Interacts with1,019 drugs
Black pepper is a common kitchen spice that is generally safe in the amounts used in food. Its extract, piperine, is mostly added to supplements to he...
BioPerine monograph & interactionsAcetyl-L-Carnitine
Interacts with203 drugs
Acetyl-L-carnitine is a form of the amino acid carnitine that the body uses to help produce energy in cells. It is most studied for nerve pain and mem...
Acetyl-L-Carnitine monograph & interactionsVitamin C
Interacts with207 drugs
Vitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for im...
Vitamin C monograph & interactionsVitamin B6
Interacts with210 drugs
Vitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is b...
Vitamin B6 monograph & interactionsCitrus Bioflavonoids
Interacts with1,169 drugs
Quercetin is a plant flavonoid with antioxidant and anti-inflammatory properties found in many common foods and sold as a supplement. While early rese...
Citrus Bioflavonoids monograph & interactionsOther (inactive) ingredients: Hydroxypropyl Methylcellulose, Bamboo Silica. These complete the product’s ingredient list but are not active constituents.
Corti-B Plex by NuMedica Drug Interactions
HelloPharmacist Interaction Report
Corti-B Plex by NuMedica contains several ingredients with documented interactions to medications.
The most serious concern is BioPerine (black pepper extract), which can increase blood levels of a number of drugs through effects on how your body absorbs and clears them. This is a Moderate-severity interaction affecting heart rhythm medications like propranolol, antiviral drugs like nevirapine, antibiotics like rifampin, seizure medications like phenytoin, and several others.
Read the full breakdown — every affected drug type, severity by severity
Vitamin B6 can reduce levels of seizure medications (phenobarbital and phenytoin) at high doses, and may add to the blood-pressure-lowering effects of antihypertensive drugs — both Moderate interactions. Vitamin C at high doses may reduce warfarin effectiveness and can increase estrogen levels from oral contraceptives or hormone replacement therapy; it may also interact with chemotherapy drugs and certain HIV medications — all Moderate.
Acetyl-L-carnitine carries Moderate-severity theoretical concerns with blood thinners like warfarin, thyroid hormone replacement, and serotonergic drugs (antidepressants and similar medications).
Pantothenic acid has no documented interactions. We could not check Quatrefolic or Citrus Bioflavonoids — we hold no interaction data for these ingredients.
Altogether, these interactions span 1,259 individual medications. Use the medication checker on this page to look up your exact drugs before starting this product.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Corti-B Plex?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Corti-B Plex interact with 1,384 drugs. Click any drug to see the details.
5 of the 7 ingredients in Corti-B Plex interact with drugs. Each result below shows which ingredient is responsible. Citrus Bioflavonoids BioPerine Vitamin B6 Vitamin C Acetyl-L-Carnitine
Ado-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with Corti-B Plex — through 2 ingredients. Tap an ingredient for the detail:
Citrus BioflavonoidsCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Citrus Bioflavonoids + Ado-trastuzumab Emtansine interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Ado-trastuzumab Emtansine interactionAbciximabReoPro
How Abciximab interacts with Corti-B Plex — through 1 ingredient. Tap an ingredient for the detail:
BioperineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Bioperine + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with Corti-B Plex — through 2 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Abemaciclib interactionCitrus BioflavonoidsCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Citrus Bioflavonoids + Abemaciclib interactionAbiraterone
How Abiraterone interacts with Corti-B Plex — through 2 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Abiraterone interactionCitrus BioflavonoidsCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Citrus Bioflavonoids + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with Corti-B Plex — through 2 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Abiraterone Acetate interactionCitrus BioflavonoidsCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Citrus Bioflavonoids + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with Corti-B Plex — through 2 ingredients. Tap an ingredient for the detail:
Citrus BioflavonoidsCytochrome P450 2c9 (cyp2c9) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2C9 substrates.
Read the full Citrus Bioflavonoids + Abrocitinib interactionBioperineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Bioperine + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with Corti-B Plex — through 2 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acalabrutinib interactionCitrus BioflavonoidsP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of P-glycoprotein substrates.
Read the full Citrus Bioflavonoids + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Corti-B Plex — through 2 ingredients. Tap an ingredient for the detail:
BioperineAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Read the full Bioperine + Acarbose interactionCitrus BioflavonoidsAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, concomitant use of quercetin and antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Citrus Bioflavonoids + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Corti-B Plex — through 2 ingredients. Tap an ingredient for the detail:
Citrus BioflavonoidsAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking quercetin with antihypertensive drugs might increase the risk of hypotension.
Read the full Citrus Bioflavonoids + Acebutolol interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Corti-B Plex — through 2 ingredients. Tap an ingredient for the detail:
Acetyl-l-carnitineAcenocoumarol (sintrom) Moderate
Interaction Summary
Theoretically, acetyl-L-carnitine might increase the anticoagulant effects of acenocoumarol.
Read the full Acetyl-l-carnitine + Acenocoumarol interactionBioperineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Bioperine + Acenocoumarol interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with Corti-B Plex — through 3 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Aspirin interactionCitrus BioflavonoidsOrganic Anion Transporter 3 (oat3) Substrates, Organic Anion Transporter 1 (oat1) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the effects and adverse effects of OAT3 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Aspirin interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with Corti-B Plex — through 3 ingredients. Tap an ingredient for the detail:
Citrus BioflavonoidsOrganic Anion Transporter 1 (oat1) Substrates, Organic Anion Transporter 3 (oat3) Substrates +1 Moderate
Interaction Summary
Theoretically, concomitant use might increase the effects and adverse effects of OAT1 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Aspirin, Caffeine interactionBioperineCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Aspirin, Caffeine interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with Corti-B Plex — through 3 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Butalbital, Caffeine interactionCitrus BioflavonoidsCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Butalbital, Caffeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with Corti-B Plex — through 3 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acetaminophen, Butalbital, Caffeine, Codeine interactionCitrus BioflavonoidsCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with Corti-B Plex — through 3 ingredients. Tap an ingredient for the detail:
Citrus BioflavonoidsCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Butalbital, Codeine interactionBioperineCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Bioperine + Acetaminophen, Butalbital, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with Corti-B Plex — through 3 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Butalbital, Codeine Phosphate interactionCitrus BioflavonoidsCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Butalbital, Codeine Phosphate interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with Corti-B Plex — through 3 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Bioperine + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionCitrus BioflavonoidsCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with Corti-B Plex — through 3 ingredients. Tap an ingredient for the detail:
Citrus BioflavonoidsCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Caffeine, Codeine interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acetaminophen, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with Corti-B Plex — through 3 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Caffeine, Codeine, Salicylamide interactionCitrus BioflavonoidsCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Caffeine, Codeine, Salicylamide interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with Corti-B Plex — through 3 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acetaminophen, Caffeine, Dihydrocodeine interactionCitrus BioflavonoidsCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Caffeine, Dihydrocodeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Caffeine, IsomethepteneMigralam
How Acetaminophen, Caffeine, Isometheptene interacts with Corti-B Plex — through 3 ingredients. Tap an ingredient for the detail:
Citrus BioflavonoidsCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Caffeine, Isometheptene interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acetaminophen, Caffeine, Isometheptene interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Isometheptene interactionAcetaminophen, Caffeine, PyrilamineMidol Max Strength Menstrual
How Acetaminophen, Caffeine, Pyrilamine interacts with Corti-B Plex — through 3 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Caffeine, Pyrilamine interactionCitrus BioflavonoidsCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Caffeine, Pyrilamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Pyrilamine interactionAcetaminophen, Chlorpheniramine Maleate, Dextromethorphan HbrVicks Formula 44M Cough, Cold & Flu Relief
How Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interacts with Corti-B Plex — through 4 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Bioperine + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionAcetyl-l-carnitineSerotonergic Drugs Moderate
Interaction Summary
Theoretically, acetyl-L-carnitine might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders, when taken with serotonergic drugs.
Read the full Acetyl-l-carnitine + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionCitrus BioflavonoidsCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with Corti-B Plex — through 4 ingredients. Tap an ingredient for the detail:
Citrus BioflavonoidsCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionBioperineCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Bioperine + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionAcetyl-l-carnitineSerotonergic Drugs Moderate
Interaction Summary
Theoretically, acetyl-L-carnitine might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders, when taken with serotonergic drugs.
Read the full Acetyl-l-carnitine + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionAcetaminophen, Chlorpheniramine, DextromethorphanCoricidin II Extra Strength Cold and Flu
How Acetaminophen, Chlorpheniramine, Dextromethorphan interacts with Corti-B Plex — through 4 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionAcetyl-l-carnitineSerotonergic Drugs Moderate
Interaction Summary
Theoretically, acetyl-L-carnitine might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders, when taken with serotonergic drugs.
Read the full Acetyl-l-carnitine + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionCitrus BioflavonoidsCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionAcetaminophen, Chlorpheniramine, Dextromethorphan HydrobromideCoricidin HBP Maximum Strength Flu
How Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interacts with Corti-B Plex — through 4 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionAcetyl-l-carnitineSerotonergic Drugs Moderate
Interaction Summary
Theoretically, acetyl-L-carnitine might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders, when taken with serotonergic drugs.
Read the full Acetyl-l-carnitine + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionCitrus BioflavonoidsCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionAcetaminophen, Chlorpheniramine, Dextromethorphan, PhenylpropanolamineMulti Symptom Cold Relief
How Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interacts with Corti-B Plex — through 4 ingredients. Tap an ingredient for the detail:
Citrus BioflavonoidsCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionBioperineCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Bioperine + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionAcetyl-l-carnitineSerotonergic Drugs Moderate
Interaction Summary
Theoretically, acetyl-L-carnitine might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders, when taken with serotonergic drugs.
Read the full Acetyl-l-carnitine + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionAcetaminophen, Chlorpheniramine, Dextromethorphan, PseudoephedrineChildren's Tylenol Cold Plus Cough, Tylenol Cold Ex Strength
How Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interacts with Corti-B Plex — through 4 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interactionAcetyl-l-carnitineSerotonergic Drugs Moderate
Interaction Summary
Theoretically, acetyl-L-carnitine might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders, when taken with serotonergic drugs.
Read the full Acetyl-l-carnitine + Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interactionCitrus BioflavonoidsCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interactionAcetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, SalicylamideRhinogesic GG
How Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interacts with Corti-B Plex — through 4 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interactionAcetyl-l-carnitineSerotonergic Drugs Moderate
Interaction Summary
Theoretically, acetyl-L-carnitine might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders, when taken with serotonergic drugs.
Read the full Acetyl-l-carnitine + Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interactionCitrus BioflavonoidsCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interactionAcetaminophen, Chlorpheniramine, PhenylephrineAlka-Seltzer PLUS, Histex SR, Protid
How Acetaminophen, Chlorpheniramine, Phenylephrine interacts with Corti-B Plex — through 4 ingredients. Tap an ingredient for the detail:
Citrus BioflavonoidsCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
Read the full Citrus Bioflavonoids + Acetaminophen, Chlorpheniramine, Phenylephrine interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acetaminophen, Chlorpheniramine, Phenylephrine interactionAcetyl-l-carnitineSerotonergic Drugs Moderate
Interaction Summary
Theoretically, acetyl-L-carnitine might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders, when taken with serotonergic drugs.
Read the full Acetyl-l-carnitine + Acetaminophen, Chlorpheniramine, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Phenylephrine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Corti-B Plex with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Citrus Bioflavonoids
Antidiabetes Drugs
Theoretically, concomitant use of quercetin and antidiabetes drugs might increase the risk of hypoglycemia.
Clinical research suggests that a combination of quercetin, myricetin, and chlorogenic acid reduce levels of fasting glucose in patients with type 2 diabetes, including those already taking antidiabetes agents. The effect of quercetin alone is unknown.
Antihypertensive Drugs
Theoretically, taking quercetin with antihypertensive drugs might increase the risk of hypotension.
Quercetin can modestly decrease blood pressure in people with mild hypertension. Theoretically, it might have additive blood pressure lowering effects when used with antihypertensive drugs.
Cyclosporine (Neoral, Sandimmune)
Theoretically, concomitant use might increase the levels and adverse effects of cyclosporine.
A small study in healthy volunteers shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of a single dose of cyclosporine, possibly due to inhibition of p-glycoprotein or cytochrome P450 3A4 (CYP3A4), which metabolizes cyclosporin.
Cytochrome P450 2C8 (Cyp2C8) Substrates
Theoretically, concomitant use might increase the levels and adverse effects of CYP2C8 substrates.
In vitro research shows that quercetin inhibits CYP2C8. Inhibition of paclitaxel (Taxol) metabolism via CYP2C8 has been reported in vitro. However, a small study in humans found no effect of quercetin on rosiglitazone (Avandia), which is also a CYP2C8 substrate.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, concomitant use might increase the levels and adverse effects of CYP2C9 substrates.
A small clinical study in healthy volunteers shows that taking quercetin 500 mg twice daily for 10 days prior to taking diclofenac, a CYP2C9 substrate, increases diclofenac plasma levels by 75% and prolongs the half-life by 32.5%. Animal research also shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of losartan (Cozaar), a substrate of CYP2C9. Furthermore, laboratory research shows that quercetin inhibits CYP2C9.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, concomitant use might increase the levels and adverse effects of CYP2D6 substrates.
In vitro research show that quercetin inhibits CYP2D6. This effect has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, concomitant use might alter the effects and adverse effects of CYP3A4 substrates.
A small clinical study in healthy volunteers shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of a single dose of cyclosporine (Neoral, Sandimmune), a substrate of CYP3A4. Animal research also shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of losartan (Cozaar) and quetiapine (Seroquel), substrates of CYP3A4. Other laboratory research also shows that quercetin inhibits CYP3A4. However, one clinical study shows that quercetin can increase the metabolism of midazolam, a substrate of CYP3A4, and decrease serum concentrations of midazolam by about 24% in some healthy individuals, suggesting possible induction of CYP3A4.
Diclofenac (Voltaren, Others)
Theoretically, concomitant use might increase the levels and adverse effects of diclofenac.
A small clinical study in healthy volunteers shows that taking quercetin 500 mg twice daily for 10 days prior to taking diclofenac increases diclofenac plasma levels by 75% and prolongs the half-life by 32.5%. This is thought to be due to inhibition of CYP2C9 by quercetin.
Losartan (Cozaar)
Theoretically, concomitant use might increase the effects and adverse effects of losartan and decrease the effects of its active metabolite.
Animal research shows that pretreatment with quercetin increases plasma levels and prolongs the half-life of losartan (Cozaar) while decreasing plasma levels of losartan's active metabolite. This metabolite, which is around 10-fold more potent than losartan, is the result of cytochrome P450 (CYP) 2C9- and CYP3A4-mediated transformation of losartan. Additionally, in vitro research shows that quercetin may inhibit P-glycoprotein-mediated efflux of losartan from the intestines, resulting in increased absorption of losartan. These results suggest that concomitant use of quercetin and losartan might increase systemic exposure to losartan while also decreasing plasma concentrations of losartan's active and more potent metabolite.
Midazolam (Versed)
Theoretically, concomitant use might decrease the levels and effects of midazolam.
A small clinical study in healthy volunteers shows that quercetin can increase the metabolism of midazolam, with a decrease in AUC of about 24%.
Mitoxantrone
Theoretically, quercetin might increase the effects and adverse effects of mitoxantrone.
In vitro research shows that quercetin increases the intracellular accumulation and cytotoxicity of mitoxantrone, possibly through inhibition of breast cancer resistance protein (BCRP), of which mitoxantrone is a substrate. So far, this interaction has not been reported in humans.
Organic Anion Transporter 1 (Oat1) Substrates
Theoretically, concomitant use might increase the effects and adverse effects of OAT1 substrates.
In vitro research shows that quercetin is a strong non-competitive inhibitor of OAT1, with half-maximal inhibitory concentration (IC50) values less than 10 mcM. So far, this interaction has not been reported in humans.
Organic Anion Transporter 3 (Oat3) Substrates
Theoretically, concomitant use might increase the effects and adverse effects of OAT3 substrates.
In vitro research shows that quercetin is a strong non-competitive inhibitor of OAT3, with half-maximal inhibitory concentration (IC50) values as low as 0.75 mcM. So far, this interaction has not been reported in humans.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Theoretically, concomitant use might increase the effects and adverse effects of OATP substrates.
In vitro evidence shows that quercetin can inhibit organic anion-transporting peptide (OATP) 1B1-mediated uptake of estrone-3-sulfate and pravastatin. Furthermore, clinical research in healthy males shows that intake of quercetin along with pravastatin increases the AUC of pravastatin by 24%, prolongs its half-life by 14%, and decreases its apparent clearance by 18%, suggesting that quercetin modestly inhibits the uptake of pravastatin in hepatic cells.
P-Glycoprotein Substrates
Theoretically, concomitant use might alter the effects and adverse effects of P-glycoprotein substrates.
There is preliminary evidence that quercetin inhibits the gastrointestinal P-glycoprotein efflux pump, which might increase the bioavailability and serum levels of drugs transported by the pump. A small study in healthy volunteers reported that pretreatment with quercetin increased bioavailability and plasma levels after a single dose of cyclosporine (Neoral, Sandimmune). Also, two small studies have shown that quercetin might decrease the absorption of talinolol, a substrate transported by the gastrointestinal P-glycoprotein efflux pump. However, in another small study, several days of quercetin treatment did not significantly affect the pharmacokinetics of saquinavir (Invirase). The reason for these discrepancies is not entirely clear. Until more is known, use quercetin cautiously in combination with P-glycoprotein substrates.
Pravastatin (Pravachol)
Theoretically, concomitant use might increase the effects and adverse effects of pravastatin.
In vitro evidence shows that quercetin can inhibit OATP 1B1-mediated uptake of pravastatin. Also, preliminary clinical research in healthy males shows that intake of quercetin along with pravastatin increases the maximum concentration of pravastatin by 24%, prolongs its half-life by 14%, and decreases its apparent clearance by 18%, suggesting that quercetin modestly inhibits the uptake of pravastatin in hepatic cells.
Prazosin (Minipress)
Theoretically, quercetin might increase the effects and adverse effects of prazosin.
In vitro research shows that quercetin inhibits the transcellular efflux of prazosin, possibly through inhibition of breast cancer resistance protein (BCRP), of which prazosin is a substrate. BCRP is an ATP-binding cassette efflux transporter in the intestines, kidneys, and liver. So far, this interaction has not been reported in humans.
Quetiapine (Seroquel)
Theoretically, concomitant use might increase the effects and adverse effects of quetiapine.
Animal research shows that pretreatment with quercetin can increase plasma levels of quetiapine and prolong its clearance, possibly due to inhibition of cytochrome P450 3A4 (CYP3A4) by quercetin. Additionally, the brain-to-plasma ratio of quetiapine concentrations increased, possibly due to inhibition of P-glycoprotein at the blood-brain barrier. This interaction has not been reported in humans.
Quinolone Antibiotics
Theoretically, concomitant use might inhibit the effects of quinolone antibiotics.
In vitro, quercetin binds to the DNA gyrase site on bacteria, which may interfere with the activity of quinolone antibiotics.
Sulfasalazine (Azulfidine)
Theoretically, quercetin might increase the effects and adverse effects of sulfasalazine.
Animal research shows that quercetin increases the maximum serum concentration (Cmax) and area under the curve (AUC) of sulfasalazine, possibly through inhibition of breast cancer resistance protein (BCRP), of which sulfasalazine is a substrate. So far, this interaction has not been reported in humans.
Warfarin (Coumadin)
Theoretically, quercetin may increase the risk of bleeding if used with warfarin.
Animal and in vitro studies show that quercetin might increase serum levels of warfarin. Quercetin and warfarin have the same human serum albumin (HSA) binding site, and in vitro research shows that quercetin has stronger affinity for the HSA binding site and can theoretically displace warfarin, causing higher serum levels of warfarin. Animal research shows that taking quercetin for 2 weeks before initiating warfarin increases the maximum serum level of warfarin by 30%, the half-life by 10%, and the overall exposure by 63% when compared with control. Concomitant administration of quercetin and warfarin, without quercetin pre-treatment, also increased these measures, but to a lesser degree. Researchers theorize that inhibition of CYP3A4 by quercetin may explain these effects. So far, this interaction has not been reported in humans.
BioPerine
Anticoagulant/Antiplatelet Drugs
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
In vitro research shows that piperine, a constituent of black pepper, seems to inhibit platelet aggregation. This has not been reported in humans.
Antidiabetes Drugs
Theoretically, black pepper might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Animal research shows that piperine, a constituent of black pepper, can reduce blood glucose levels. Monitor blood glucose levels closely. Dose adjustments might be necessary.
Atorvastatin (Lipitor)
Theoretically, black pepper might increase blood levels of atorvastatin.
Animal research shows that taking piperine, a constituent of black pepper, 35 mg/kg can increase the maximum serum concentration of atorvastatin three-fold. This has not been reported in humans.
Cyclosporine (Neoral, Sandimmune)
Theoretically, black pepper might increase the effects and side effects of cyclosporine.
In vitro research shows that piperine, a constituent of black pepper, increases the bioavailability of cyclosporine. This has not been reported in humans.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
In vitro research suggests that some constituents of black pepper inhibit CYP2D6. This has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
In vitro research and pharmacokinetic simulation data suggest that piperine, a constituent of black pepper, as well as the pepper fruit seem to inhibit CYP3A4. This has not been reported in humans.
Lithium
Theoretically, black pepper might increase blood levels of lithium due to its diuretic effects. The dose of lithium might need to be reduced.
Black pepper is thought to have diuretic properties.
Nevirapine (Viramune)
Black pepper might increase blood levels of nevirapine.
Clinical research shows that piperine, a constituent of black pepper, increases the plasma concentration of nevirapine. However, no adverse effects were observed in this study.
P-Glycoprotein Substrates
Theoretically, black pepper might increase levels of P-glycoprotein substrates.
In vitro research shows that piperine, a constituent of black pepper, seems to inhibit P-glycoprotein.
Pentobarbital (Nembutal)
Theoretically, black pepper might increase the sedative effects of pentobarbital.
Animal research shows that piperine, a constituent of black pepper, increases pentobarbital-induced sleeping time.
Phenytoin (Dilantin)
Black pepper might increase blood levels of phenytoin.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption, slow elimination, and increase levels of phenytoin. Taking a single dose of black pepper 1 gram along with phenytoin seems to double the serum concentration of phenytoin. Consuming a soup with black pepper providing piperine 44 mg/200 mL of soup along with phenytoin also seems to increase phenytoin levels when compared with consuming the same soup without black pepper.
Propranolol (Inderal)
Black pepper might increase blood levels of propranolol.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and slow elimination of propranolol.
Rifampin (Rifadin)
Black pepper might increase blood levels of rifampin.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and serum levels of rifampin.
Theophylline
Black pepper might increase blood levels of theophylline.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and slow elimination of theophylline.
Amoxicillin (Amoxil, Trimox)
Theoretically, black pepper might increase the effects and side effects of amoxicillin.
Animal research shows that taking piperine, a constituent of black pepper, with amoxicillin increases plasma levels of amoxicillin. This has not been reported in humans.
Carbamazepine (Tegretol)
Theoretically, black pepper might increase blood levels of carbamazepine, potentially increasing the effects and side effects of carbamazepine.
One clinical study in patients taking carbamazepine 300 mg or 500 mg twice daily shows that taking a single 20 mg dose of purified piperine, a constituent of black pepper, increases carbamazepine levels. Piperine may increase carbamazepine absorption by increasing blood flow to the GI tract, increasing the surface area of the small intestine, or inhibiting cytochrome P450 3A4 (CYP3A4) in the gut wall. Absorption was significantly increased by 7-10 mcg/mL/hour. The time to eliminate carbamazepine was also increased by 4-8 hours. Although carbamazepine levels were increased, this did not appear to increase side effects. In vitro research also shows that piperine can increase carbamazepine levels by 11% in a time-dependent manner.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
In vitro research suggests that black pepper induces CYP1A2. This has not been reported in humans.
Vitamin B6
Amiodarone (Cordarone)
Theoretically, vitamin B6 might increase the photosensitivity caused by amiodarone.
Despite initial case reports suggesting that pyridoxine may have a protective effect against amiodarone-induced photosensitivity, preliminary clinical research suggests that pyridoxine may actually exacerbate this adverse effect.
Antihypertensive Drugs
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Research in hypertensive rats shows that vitamin B6 can decrease systolic blood pressure. Similarly, clinical research in patients with hypertension shows that taking high doses of vitamin B6 may reduce systolic and diastolic blood pressure, possibly by reducing plasma levels of epinephrine and norepinephrine.
Phenobarbital (Luminal)
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenobarbital, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenobarbital to avoid high doses of vitamin B6.
Phenytoin (Dilantin)
High doses of vitamin B6 may reduce the levels and clinical effects of phenytoin.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenytoin, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenytoin to avoid high doses of vitamin B6.
Levodopa
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Vitamin B6 (pyridoxine) enhances the metabolism of levodopa, reducing its clinical effects. However, this interaction does not occur when carbidopa is used concurrently with levodopa (Sinemet). Therefore, it is not likely to be a problem in most people.
Vitamin C
Alkylating Agents
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin C have on chemotherapy.
Aluminum
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Research in animals and humans shows that vitamin C increases aluminum absorption, theoretically by chelating aluminum and keeping it in solution where it is available for absorption. In people with normal renal function, urinary excretion of aluminum will likely increase, making aluminum retention and toxicity unlikely. Patients with renal failure who take aluminum-containing compounds such as phosphate binders should avoid vitamin C supplements in doses above the recommended dietary allowances.
Antitumor Antibiotics
Theoretically, the antioxidant effects of vitamin C might reduce the effectiveness of antitumor antibiotics.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as doxorubicin. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effects, if any, antioxidants such as vitamin C have on chemotherapy.
Estrogens
Vitamin C might increase blood levels of estrogens.
Increases in plasma estrogen levels of up to 55% occur under some circumstances when vitamin C is taken concurrently with oral contraceptives or hormone replacement therapy, including topical products. It is suggested that vitamin C prevents oxidation of estrogen in the tissues, regenerates oxidized estrogen, and reduces sulfate conjugation of estrogen in the gut wall. When tissue levels of vitamin C are high, these processes are already maximized and supplemental vitamin C does not have any effect on estrogen levels. Increases in plasma estrogen levels may occur when patients who are deficient in vitamin C take supplements. Monitor these patients for estrogen-related side effects.
Fluphenazine (Prolixin)
Theoretically, vitamin C might decrease levels of fluphenazine.
In one patient there was a clinically significant decrease in fluphenazine levels when vitamin C (500 mg twice daily) was started. The mechanism is not known, and there is no further data to confirm this interaction.
Indinavir (Crixivan)
Vitamin C can modestly reduce indinavir levels.
One pharmacokinetic study shows that taking vitamin C 1 gram orally once daily along with indinavir 800 mg orally three times daily reduces the area under the concentration-time curve of indinavir by 14%. The mechanism of this interaction is unknown, but it is unlikely to be clinically significant in most patients. The effect of higher doses of vitamin C on indinavir levels is unknown.
Levothyroxine (Synthroid, Others)
Vitamin C can increase levothyroxine absorption.
Two clinical studies in adults with poorly controlled hypothyroidism show that swallowing levothyroxine with a glass of water containing vitamin C 500-1000 mg in solution reduces thyroid stimulating hormone (TSH) levels and increases thyroxine (T4) levels when compared with taking levothyroxine alone. This suggests that vitamin C increases the oral absorption of levothyroxine, possibly due to a reduction in pH.
Warfarin (Coumadin)
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Vitamin C in high doses may cause diarrhea and possibly reduce warfarin absorption. There are reports of two people who took up to 16 grams daily of vitamin C and had a reduction in prothrombin time. Lower doses of 5-10 grams daily can also reduce warfarin absorption. In many cases, this does not seem to be clinically significant. However, a case of warfarin resistance has been reported for a patient who took vitamin C 500 mg twice daily. Cessation of vitamin C supplementation resulted in a rapid increase in international normalized ratio (INR). Tell patients taking warfarin to avoid taking vitamin C in excessively high doses (greater than 10 grams daily). Lower doses may be safe, but the anticoagulation activity of warfarin should be monitored. Patients who are stabilized on warfarin while taking vitamin C should avoid adjusting vitamin C dosage to prevent the possibility of warfarin resistance.
Acetaminophen (Tylenol, Others)
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
A small pharmacokinetic study in healthy volunteers shows that taking high-dose vitamin C (3 grams) 1.5 hours after taking acetaminophen 1 gram slightly increases the apparent half-life of acetaminophen from around 2.3 hours to 3.1 hours. Ascorbic acid competitively inhibits sulfate conjugation of acetaminophen. However, to compensate, elimination of acetaminophen glucuronide and unconjugated acetaminophen increases. This effect is not likely to be clinically significant.
Aspirin
Acidification of the urine by vitamin C might increase aspirin levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction is not clinically significant.
Choline Magnesium Trisalicylate (Trilisate)
Acidification of the urine by vitamin C might increase choline magnesium trisalicylate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Niacin
Vitamin C might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as vitamin C, or to the combination. It also is not known whether it will occur in other patient populations.
Salsalate (Disalcid)
Acidification of the urine by vitamin C might increase salsalate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams/day vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Acetyl-L-Carnitine
Acenocoumarol (Sintrom)
Theoretically, acetyl-L-carnitine might increase the anticoagulant effects of acenocoumarol.
L-carnitine, the parent compound of acetyl-L-carnitine, might enhance the anticoagulant effects of acenocoumarol, an oral anticoagulant that is similar to warfarin, but shorter-acting. There are at least two case reports of INR elevation when L-carnitine was taken with acenocoumarol. In one case, a 33-year-old male with a previously stable INR had an elevated INR of 4.65 after L-carnitine was started and continued for 10 weeks. INR normalized after discontinuation of the L-carnitine-containing product. It is unclear if such an interaction would also occur with acetyl-L-carnitine.
Serotonergic Drugs
Theoretically, acetyl-L-carnitine might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders, when taken with serotonergic drugs.
Animal research shows that acetyl-L-carnitine can increase levels of serotonin in the brain.
Thyroid Hormone
Theoretically, acetyl-L-carnitine might decrease the effectiveness of thyroid hormone replacement.
L-carnitine appears to act as a peripheral thyroid hormone antagonist by inhibiting entry of thyroid hormone into the nucleus of cells. Taking L-carnitine also seems to diminish some of the symptoms of hyperthyroidism. It is unclear if such an interaction would occur with acetyl-L-carnitine.
Warfarin (Coumadin)
Theoretically, acetyl-L-carnitine might increase the anticoagulant effects of warfarin.
L-carnitine, the parent compound of acetyl-L-carnitine, might increase the anticoagulant effects of acenocoumarol, a shorter-acting oral anticoagulant similar to warfarin. There is not enough information to know whether this interaction occurs with acetyl-L-carnitine and warfarin.
Brand information
Manufacturer and brand details for Corti-B Plex, from the product label.
NuMedica
See all NuMedica products- Name
- NuMedica LLC
- Street Address
- 9503 E. 55th Place
- City
- Tulsa
- State
- OK
- ZipCode
- 74145
- Phone Number
- 800.869.8100
- Web Address
- www.numedica.com
Corti-B Plex by NuMedica: Common Questions
Does Corti-B Plex by NuMedica interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
What is BioPerine and why is it in this product?
Can I take this if I'm on birth control or hormone therapy?
Is it safe to take this long-term?
What should I do if I'm taking seizure medication?
Does this product have any fillers?
Can I take this while pregnant or breastfeeding?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Corti-B Plex is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Corti-B Plex’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Pantothenic Acid
Pantothenic acid is vitamin B5, an essential nutrient your body uses to turn food into energy. True deficiency is very rare because it is found in nearly all foods, and most people meet thei...
Read the full Pantothenic Acid monograph → Herb & supplement monographBlack Pepper
Interacts with 1,019 drugsBlack pepper is a common kitchen spice that is generally safe in the amounts used in food. Its extract, piperine, is mostly added to supplements to help the body absorb other ingredients (li...
Read the full Black Pepper monograph → Herb & supplement monographAcetyl-l-carnitine
Interacts with 203 drugsAcetyl-L-carnitine is a form of the amino acid carnitine that the body uses to help produce energy in cells. It is most studied for nerve pain and memory-related conditions, though the evide...
Read the full Acetyl-l-carnitine monograph → Herb & supplement monographVitamin C
Interacts with 207 drugsVitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for immune function, collagen, and acts as an...
Read the full Vitamin C monograph → Herb & supplement monographVitamin B6
Interacts with 210 drugsVitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is best known for helping with pregnancy-rel...
Read the full Vitamin B6 monograph → Herb & supplement monographQuercetin
Interacts with 1,169 drugsQuercetin is a plant flavonoid with antioxidant and anti-inflammatory properties found in many common foods and sold as a supplement. While early research is interesting for allergies, blood...
Read the full Quercetin monograph →Sources & How We Checked
Corti-B Plex's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 171 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Pantothenic Acid 11 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Debourdeau PM, Djezzar S, Estival JL, et al. Life-threatening eosinophilic pleuropericardial effusion related to vitamins B5 and H. Ann Pharmacother 2001;35:424-6. DOI
- Schmuth, M., Wimmer, M. A., Hofer, S., Sztankay, A., Weinlich, G., Linder, D. M., Elias, P. M., Fritsch, P. O., and Fritsch, E. Topical corticosteroid therapy for acute radiation dermatitis: a prospective, randomized, double-blind study. Br.J.Dermatol. 2 PubMed
- Schreck, U., Paulsen, F., Bamberg, M., and Budach, W. Intraindividual comparison of two different skin care conceptions in patients undergoing radiotherapy of the head-and-neck region. Creme or powder? Strahlenther.Onkol. 2002;178(6):321-329. PubMed
- Herbst, R. A., Uter, W., Pirker, C., Geier, J., and Frosch, P. J. Allergic and non-allergic periorbital dermatitis: patch test results of the Information Network of the Departments of Dermatology during a 5-year period. Contact Dermatitis 2004;51(1):13-1 PubMed
- Champault, G. and Patel, J. C. [Treatment of constipation with Bepanthene]. Med.Chir Dig. 1977;6(1):57-59.
- Scott LN, Fiume M, Bergfeld WF, et al. Safety Assessment of Panthenol, Pantothenic Acid, and Derivatives as Used in Cosmetics. Int J Toxicol 2022;41(3_suppl):77-128. PubMed
- Han J, Warshaw EM. Allergic Contact Dermatitis to Panthenol in "Hypoallergenic" Products. Dermatitis 2023;34(1):62-63. PubMed
- Blanchard G, Kerre S, Walker A, et al. Allergic contact dermatitis from pantolactone and dexpanthenol in wound healing creams. Contact Dermatitis 2022;87(5):468-471. PubMed
- Peltier E, Trapp S, de Salvo R, et al. A new dexpanthenol-containing liquid cleanser for atopic-prone skin: Results from two prospective clinical studies evaluating cutaneous tolerability, moisturization potential, and effects on barrier function. J Cosme PubMed
Black Pepper 29 references
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
- Bano G, Amla V, Raina RK, et al. The effect of piperine on pharmacokinetics of phenytoin in healthy volunteers. Planta Med 1987;53:568-9. PubMed
- Bano G, et al. Effect of piperine on bioavailability and pharmacokinetics of propranolol and theophylline in healthy volunteers. Eur J Clin Pharmacol 1991;41;615-7. PubMed
- Cohle SD, Trestrail JD III, Graham MA, et al. Fatal pepper aspiration. Am J Dis Child 1988;142:633-6. PubMed
- Bhardwaj RK, Glaeser H, Becquemont L, et al. Piperine, a major constituent of black pepper, inhibits human P-glycoprotein and CYP3A4. J Pharmacol Exp Ther 2002;302:645-50. PubMed
- Velpandian T, Jasuja R, Bhardwaj RK, et al. Piperine in food: interference in the pharmacokinetics of phenytoin. Eur J Drug Metab Pharmacokinet 2001;26:241-7. PubMed
- Pattanaik S, Hota D, Prabhakar S, et al. Pharmacokinetic interaction of a single dose of piperine with steady-state carbamazepine in epilepsy patients. Phytother Res 2009;23:1281-6.
- Munakata, M., Kobayashi, K., Niisato-Nezu, J., Tanaka, S., Kakisaka, Y., Ebihara, T., Ebihara, S., Haginoya, K., Tsuchiya, S., and Onuma, A. Olfactory stimulation using black pepper oil facilitates oral feeding in pediatric patients receiving long-term en
- Myers, B. M., Smith, J. L., and Graham, D. Y. Effect of red pepper and black pepper on the stomach. Am J Gastroenterol 1987;82(3):211-214.
- Raghavendra, R. H. and Naidu, K. A. Spice active principles as the inhibitors of human platelet aggregation and thromboxane biosynthesis. Prostaglandins Leukot.Essent.Fatty Acids 2009;81(1):73-78. PubMed
- Subehan, Usia, T., Kadota, S., and Tezuka, Y. Mechanism-based inhibition of human liver microsomal cytochrome P450 2D6 (CYP2D6) by alkamides of Piper nigrum. Planta Med 2006;72(6):527-532.
- Kasibhatta, R. and Naidu, M. U. Influence of piperine on the pharmacokinetics of nevirapine under fasting conditions: a randomised, crossover, placebo-controlled study. Drugs R.D. 2007;8(6):383-391. PubMed
- Usia, T., Iwata, H., Hiratsuka, A., Watabe, T., Kadota, S., and Tezuka, Y. CYP3A4 and CYP2D6 inhibitory activities of Indonesian medicinal plants. Phytomedicine. 2006;13(1-2):67-73. PubMed
- Mujumdar, A. M., Dhuley, J. N., Deshmukh, V. K., Raman, P. H., Thorat, S. L., and Naik, S. R. Effect of piperine on pentobarbitone induced hypnosis in rats. Indian J Exp.Biol. 1990;28(5):486-487.
- Panda, S. and Kar, A. Piperine lowers the serum concentrations of thyroid hormones, glucose and hepatic 5'D activity in adult male mice. Horm.Metab Res. 2003;35(9):523-526. PubMed
- Lawless, H. and Stevens, D. A. Effects of oral chemical irritation on taste. Physiol Behav. 1984;32(6):995-998. PubMed
- Hiwale, A. R., Dhuley, J. N., and Naik, S. R. Effect of co-administration of piperine on pharmacokinetics of beta-lactam antibiotics in rats. Indian J Exp.Biol. 2002;40(3):277-281.
- Han, Y., Chin Tan, T. M., and Lim, L. Y. In vitro and in vivo evaluation of the effects of piperine on P-gp function and expression. Toxicol.Appl.Pharmacol. 8-1-2008;230(3):283-289. PubMed
- Sharma, P., Varma, M. V., Chawla, H. P., and Panchagnula, R. In situ and in vivo efficacy of peroral absorption enhancers in rats and correlation to in vitro mechanistic studies. Farmaco 2005;60(11-12):874-883. PubMed
- Aher, S., Biradar, S., Gopu, C. L., and Paradkar, A. Novel pepper extract for enhanced P-glycoprotein inhibition. J Pharm.Pharmacol. 2009;61(9):1179-1186. PubMed
- Zutshi, R. K., Singh, R., Zutshi, U., Johri, R. K., and Atal, C. K. Influence of piperine on rifampicin blood levels in patients of pulmonary tuberculosis. J Assoc.Physicians India 1985;33(3):223-224.
- Marotta, R. B. and Floch, M. H. Diet and nutrition in ulcer disease. Med Clin North Am 1991;75(4):967-979. PubMed
- Subehan, Usia, T., Iwata, H., Kadota, S., and Tezuka, Y. Mechanism-based inhibition of CYP3A4 and CYP2D6 by Indonesian medicinal plants. J Ethnopharmacol. 5-24-2006;105(3):449-455. PubMed
- Gimenez L, Zacharisen M. Severe pepper allergy in a young child. WMJ. 2011 Jun;110(3):138-9.
- Ren T, Yang M, Xiao M, Zhu J, Xie W, Zuo Z. Time-dependent inhibition of carbamazepine metabolism by piperine in anti-epileptic treatment. Life Sci. 2019;218:314-323. PubMed
- Thomas AB, Choudhary DC, Raje A, Nagrik SS. Pharmacokinetics and pharmacodynamic herb-drug interaction of piperine with atorvastatin in rats. J Chromatogr Sci 2021;59(4):371-80. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Lin F, Hu Y, Zhang Y, Zhao L, Zhong D, Liu J. Predicting Food-Drug Interactions between Piperine and CYP3A4 Substrate Drugs Using PBPK Modeling. Int J Mol Sci 2024;25(20):10955. PubMed
Acetyl-l-carnitine 22 references
- Thal LJ, Carta A, Clarke WR, et al. A 1-year multicenter placebo-controlled study of acetyl-L-carnitine in patients with Alzheimer's Disease. Neurology 1996;47:705-11. PubMed
- Sano M, Bell K, Cote L, et al. Double-blind parallel design pilot study of acetyl levocarnitine in patients with Alzheimer's Disease. Arch Neurol 1992;49:1137-41. PubMed
- Spagnoli A, Lucca U, Menasce G, et al. Long-term acetyl-L-carnitine treatment in Alzheimer's Disease. Neurology 1991;41:1726-32. PubMed
- Brooks JO 3rd, Yesavage JA, Carta A, Bravi D. Acetyl L-carnitine slows decline in younger patients with Alzheimer's disease: a reanalysis of a double-blind, placebo-controlled study using the trilinear approach. Int Psychoger 1998;10:193-203. PubMed
- Pettegrew JW, Klunk WE, Panchalingam K, et al. Clinical and neurochemical effects of acetyl-L-carnitine in Alzheimer's disease. Neurobiol Aging 1995;16:1-4. PubMed
- Rai G, Wright G, Scott L, et al. Double-blind, placebo controlled study of acetyl-l-carnitine in patients with Alzheimer's dementia. Curr Med Res Opin 1990;11:638-47. PubMed
- Benvenga S, Ruggeri RM, Russo A, et al. Usefulness of L-carnitine, a naturally occurring peripheral antagonist of thyroid hormone action, in iatrogenic hyperthyroidism: a randomized, double-blind, placebo-controlled clinical trial. J Clin Endocrinol Meta
- Montgomery SA, Thal LJ, Amrein R. Meta-analysis of double blind randomized controlled clinical trials of acetyl-L-carnitine versus placebo in the treatment of mild cognitive impairment and mild Alzheimer's disease. Int Clin Psychopharmacol 2003;18:61-71.. PubMed
- Martinez E, Domingo P, Roca-Cusachs A. Potentiation of acenocoumarol action by L-carnitine. J Intern Med 1993;233:94.
- Hudson S, Tabet N. Acetyl-L-carnitine for dementia. Cochrane Database Syst Rev 2003;2:CD003158.. PubMed
- Bachmann HU, Hoffmann A. Interaction of food supplement L-carnitine with oral anticoagulant acenocoumarol. Swiss Med Wkly 2004;134:385. PubMed
- De Grandis D, Minardi C. Acetyl-L-carnitine (levacecarnine) in the treatment of diabetic neuropathy. A long-term, randomised, double-blind, placebo-controlled study. Drugs R D 2002;3:223-31. PubMed
- 12761 Benvenga S, Amato A, Calvani M, Trimarchi F. Effects of carnitine on thyroid hormone action. Ann N Y Acad Sci 2004;1033:158-67. PubMed
- Sima AAF, Calvani M, Mehra M, et al. Acetyl-L-carnitine improves pain, nerve regeneration, and vibratory perception in patients with chronic diabetic neuropathy: An analysis of two randomized, placebo-controlled trials. Diabetes Care 2005;28:89-94.
- Youle, M. and Osio, M. A double-blind, parallel-group, placebo-controlled, multicentre study of acetyl L-carnitine in the symptomatic treatment of antiretroviral toxic neuropathy in patients with HIV-1 infection. HIV.Med. 2007;8(4):241-250.
- Brennan BP, Jensen JE, Hudson JI, Coit CE, Beaulieu A, Pope HG Jr, Renshaw PF, Cohen BM. A placebo-controlled trial of acetyl-L-carnitine and a-lipoic acid in the treatment of bipolar depression. J Clin Psychopharmacol. 2013 Oct;33(5):627-35.
- Ledinek AH, Sajko MC, Rot U. Evaluating the effects of amantadin, modafinil and acetyl-L-carnitine on fatigue in multiple sclerosis--result of a pilot randomized, blind study. Clin Neurol Neurosurg. 2013 Dec;115 Suppl 1:S86-9. PubMed
- Martinotti G, Andreoli S, Reina D, Di Nicola M, Ortolani I, Tedeschi D, Fanella F, Pozzi G, Iannoni E, D'Iddio S, Prof LJ. Acetyl-l-Carnitine in the treatment of anhedonia, melancholic and negative symptoms in alcohol dependent subjects. Prog Neuropsychop PubMed
- Baek SM, Zheng R, Seo EJ, Hwang DY, Kim BH. Pharmacokinetic comparisons of two acetyl-L-carnitine formulations in healthy Korean volunteers. Int J Clin Pharmacol Ther. 2015;53(11):980-6. PubMed
- Goodison G, Overeem K, de Monte V, Siskind D. Mania associated with self-prescribed acetyl-l-carnitine in a man with bipolar I disorder. Australas Psychiatry. 2017;25(1):13-4.
- Bruno A, Pandolfo G, Crucitti M, Lorusso S, Zoccali RA, Muscatello MR. Acetyl-L-Carnitine Augmentation of Clozapine in Partial-Responder Schizophrenia: A 12-Week, Open-Label Uncontrolled Preliminary Study. Clin Neuropharmacol. 2016;39(6):277-80. PubMed
- Veronese N, Stubbs B, Solmi M, Ajnakina O, Carvalho AF, Maggi S. Acetyl-L-Carnitine Supplementation and the Treatment of Depressive Symptoms: A Systematic Review and Meta-Analysis. Psychosom Med. 2018;80(2):154-9. PubMed
Vitamin C 51 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Back DJ, Breckenridge AM, MacIver M, et al. Interaction of ethinyloestradiol with ascorbic acid in man. Br Med J (Clin Res Ed) 1981;282:1516.
- Morris JC, Beeley L, Ballantine N. Interaction of ethinyloestradiol with ascorbic acid in man [letter]. Br Med J (Clin Res Ed) 1981;283:503.
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Dwyer JH, Merz NB, Shirocre AM, et al. Progression of early atherosclerosis and intake of vitamin C and vitamin E from supplements and food. The Los Angeles Atherosclerosis Study. 41st Annual Conference on Cardiovascular Disease Epidemiology and Prevent
- Levine M, Rumsey SC, Daruwala R, et al. Criteria and recommendations for vitamin C intake. JAMA 1999;281:1415-23. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Houston JB, Levy G. Drug biotransformation interactions in man VI: Acetaminophen and ascorbic acid. J Pharm Sci 1976;65:1218-21. PubMed
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Rosenthal G. Interaction of ascorbic acid and warfarin. JAMA 1971;215:1671. DOI
- Hume R, Johnstone JM, Weyers E. Interaction of ascorbic acid and warfarin. JAMA 1972;219:1479. DOI
- Smith EC, Skalski RJ, Johnson GC, Rossi GV. Interaction of ascorbic acid and warfarin. JAMA 1972;221:1166. DOI
- Traxer O, Huet B, Poindexter J, et al. Effect of ascorbic acid consumption on urinary stone risk factors. J Urol 2003;170:397-401.. PubMed
- Domingo JL, Gomez M, Llobet JM, Richart C. Effect of ascorbic acid on gastrointestinal aluminum absorption (letter). Lancet 1991;338:1467.
- Domingo JL, Gomez M, Llobet JM, Corbella J. Influence of some dietary constituents on aluminum absorption and retention in rats. Kidney Int 1991;39:598-601. PubMed
- Partridge NA, Regnier FE, White JL, Hem SL. Influence of dietary constituents on intestinal absorption of aluminum. Kidney Int 1989;35:1413-7. PubMed
- Mc Leod DC, Nahata MC. Inefficacy of ascorbic acid as a urinary acidifier (letter). N Engl J Med 1977;296:1413. DOI
- Hansten PD, Hayton WL. Effect of antacid and ascorbic acid on serum salicylate concentration. J Clin Pharmacol 1980;20:326-31. PubMed
- Dysken MW, Cumming RJ, Channon RA, Davis JM. Drug interaction between ascorbic acid and fluphenazine. JAMA 1979;241:2008. DOI
- Vihtamaki T, Parantainen J, Koivisto AM, et al. Oral ascorbic acid increases plasma oestradiol during postmenopausal hormone replacement therapy. Maturitas 2002;42:129-35. PubMed
- Slain D, Amsden JR, Khakoo RA, et al. Effect of high-dose vitamin C on the steady-state pharmacokinetics of the protease inhibitor indinavir in healthy volunteers. Pharmacotherapy 2005;25:165-70. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Feetam CL, Leach RH, Meynell MJ. Lack of a clinically important interaction between warfarin and ascorbic acid. Toxicol Appl Pharmacol 1975;31:544-7. PubMed
- Weintraub M, Griner PF. Warfarin and ascorbic acid: lack of evidence for a drug interaction. Toxicol Appl Pharmacol 1974;28:53-6. PubMed
- Lee DH, Folsom AR, Harnack L, et al. Does supplemental vitamin C increase cardiovascular disease risk in women with diabetes? Am J Clin Nutr 2004;80:1194-200. PubMed
- Taylor EN, Stampfer MJ, Curhan GC. Dietary factors and the risk of incident kidney stones in men: new insights after 14 years of follow-up. J Am Soc Nephrol 2004;15:3225-32. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Fairweather-Tait S, Hickson K, McGaw B, et al. Orange juice enhances aluminium absorption from antacid preparation. Eur J Clin Nutr. 1994;48(1):71-3.
- Gruenwald, J., Graubaum, H. J., Busch, R., and Bentley, C. Safety and tolerance of ester-C compared with regular ascorbic acid. Adv.Ther. 2006;23(1):171-178.
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Einerson, B., Nathorn, C., Kitiyakara, C., Sirada, M., and Thamlikitkul, V. The efficacy of ascorbic acid in suboptimal responsive anemic hemodialysis patients receiving erythropoietin: a meta-analysis. J Med.Assoc.Thai. 2011;94 Suppl 1:S134-S146.
- Li, G., Li, L., Yu, C., and Chen, L. Effect of vitamins C and E supplementation on Helicobacter pylori eradication: a meta-analysis. Br.J Nutr 2011;106(11):1632-1637.
- Chen X, Shen L, Gu X, et al. High-dose supplementation with vitamin C--induced pediatric urolithiasis: the first case report in a child and literature review. Urology. 2014;84(4):922-4. PubMed
- Sattar A, Willman JE, Kolluri R. Possible warfarin resistance due to interaction with ascorbic acid: case report and literature review. Am J Health Syst Pharm. 2013;70(9):782-6. PubMed
- Yaich S, Chaabouni Y, Charfeddine K, et al. Secondary oxalosis due to excess vitamin C intake: a cause of graft loss in a renal transplant recipient. Saudi J Kidney Dis Transpl. 2014;25(1):113-6. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Rumbold A, Ota E, Nagata C, Shahrook S, Crowther CA. Vitamin C supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004072. PubMed
- Seo MS, Kim JK, Shim JY. High-dose vitamin C promotes regression of multiple pulmonary metastases originating from hepatocellular carcinoma. Yonsei Med J. 2015;56(5):1449-52. PubMed
- Skelin M, Lucijanic T, Amidzic Klaric D, et al. Factors Affecting Gastrointestinal Absorption of Levothyroxine: A Review. Clin Ther. 2017 Feb;39(2):378-403. PubMed
- Jiang K, Tang K, Liu H, Xu H, Ye Z, Chen Z. Ascorbic acid supplements and kidney stones incidence among men and women: a systematic review and meta-analysis. Urol J. 2019;16(2):115-120.
- Thomas S, Patel D, Bittel B, et al. Effect of High-Dose Zinc and Ascorbic Acid Supplementation vs Usual Care on Symptom Length and Reduction Among Ambulatory Patients With SARS-CoV-2 Infection: The COVID A to Z Randomized Clinical Trial. JAMA Netw Open. 2 PubMed
- Giffen MA, McLemore JL. Hyperoxalosis Secondary to Intravenous Vitamin C Administration as a Non-Allopathic Treatment for Cancer. Acad Forensic Pathol 2019;9(1-2):118-126. PubMed
- Maike A, Sturgill D, Gallan A. Oxalate Nephropathy in a Renal Transplant Recipient After Receiving High Dose Ascorbic Acid. Am J Med Sci 2021. PubMed
- Shen ZY, Chen YR, Wang MC, Chang SS. High-dose vitamin C-induced acute oxalate nephropathy in a renal transplant recipient: a case report and literature review. Asian J Surg 2022. PubMed
- Yanase F, Spano S, Maeda A, et al. Mega-dose sodium ascorbate: a pilot, single-dose, physiological effect, double-blind, randomized, controlled trial. Crit Care 2023;27(1):371. PubMed
- Sharma Y, Sumanadasa S, Shahi R, et al. Efficacy and safety of vitamin C supplementation in the treatment of community-acquired pneumonia: a systematic review and meta-analysis with trial sequential analysis. Sci Rep 2024;14(1):11846. PubMed
- Pejcic AV, Petrovic NZ, Djordjic MD, Milosavljevic MN. Vitamin C Levels in Pregnant Women and the Efficacy of Vitamin C Supplements in Preventing Premature Rupture of Membranes: A Systematic Review and Meta-Analysis. Balkan Med J 2024;41(4):248-260. PubMed
Vitamin B6 32 references
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Geerling BJ, Dagnelie PC, Badart-Smook A, et al. Diet as a risk factor for the development of ulcerative colitis. Am J Gastroenterol 2000;95:1008-13. PubMed
- South M. Neonatal seizures after pyridoxine use -- reply. Lancet 1999;354:2083. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Baxter P, Aicardi J. Neonatal seizures after pyridoxine use. Lancet 1999;354:2082-3. PubMed
- Bendich A, Cohen M. Vitamin B6 safety issues. Ann N Y Acad Sci 1990;585:321-30.
- Schaumburg H, Kaplan J, Windebank A. Sensory neuropathy from pyridoxine abuse. A new megavitamin syndrome. N Engl J Med 1983;309:445-8. PubMed
- Gordon N. Pyridoxine dependency: an update. Dev Med Child Neurol 1997;39:63-5. PubMed
- Lewis PJ. Pain in the hand and wrist. Pyridoxine supplements may help patients with carpal tunnel syndrome. BMJ 1995;310:1534. PubMed
- Kaufman G. Pyridoxine against amiodarone-induced photosensitivity (letter). Lancet 1984;1:51-2. PubMed
- Mulrow JP, Mulrow CD, McKenna WJ. Pyridoxine and amiodarone-induced photosensitivity. Ann Intern Med 1985;103:68-9. PubMed
- Kawada A, Kashima A, Shiraishi H, et al. Pyridoxine-induced photosensitivity and hypophosphatasia. Dermatology 2000;201:356-60.. PubMed
- Vasile A, Goldberg R, Kornberg B. Pyridoxine toxicity: report of a case. J Am Osteopath Assoc 1984;83:790-1. DOI
- Hansson O, Sillanpaa M. Pyridoxine and serum concentration of phenytoin and phenobarbitone. Lancet 1976;1:256. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Chittumma P, Kaewkiattikun K, Wiriyasiriwach B. Comparison of the effectiveness of ginger and vitamin B6 for treatment of nausea and vomiting in early pregnancy: a randomized double-blind controlled trial. J Med Assoc Thai 2007;90:15-20.
- Hatzitolios, A., Iliadis, F., Katsiki, N., and Baltatzi, M. Is the anti-hypertensive effect of dietary supplements via aldehydes reduction evidence based? A systematic review. Clin Exp.Hypertens. 2008;30(7):628-639. PubMed
- Vasdev, S., Ford, C. A., Parai, S., Longerich, L., and Gadag, V. Dietary vitamin B6 supplementation attenuates hypertension in spontaneously hypertensive rats. Mol.Cell Biochem. 1999;200(1-2):155-162.
- de, Vogel S., Dindore, V., van, Engeland M., Goldbohm, R. A., van den Brandt, P. A., and Weijenberg, M. P. Dietary folate, methionine, riboflavin, and vitamin B-6 and risk of sporadic colorectal cancer. J Nutr 2008;138(12):2372-2378. PubMed
- Hagen, I., Nesheim, B. I., and Tuntland, T. No effect of vitamin B-6 against premenstrual tension. A controlled clinical study. Acta Obstet.Gynecol.Scand. 1985;64(8):667-670. PubMed
- Aybak, M., Sermet, A., Ayyildiz, M. O., and Karakilcik, A. Z. Effect of oral pyridoxine hydrochloride supplementation on arterial blood pressure in patients with essential hypertension. Arzneimittelforschung. 1995;45(12):1271-1273.
- Lal, K. J., Dakshinamurti, K., and Thliveris, J. The effect of vitamin B6 on the systolic blood pressure of rats in various animal models of hypertension. J Hypertens. 1996;14(3):355-363. PubMed
- Lauritzen CH, Reuter HD, Repges R, Bohnert K, and Schmidt U. Treatment of premenstrual tension syndrome with Vitex agnus castus. Controlled, double-blind study versus pyridoxine. Phytomed 1997;4(3):183-189. PubMed
- Fonseca VA, Lavery LA, Thethi TK, et al. Metanx in type 2 diabetes with peripheral neuropathy: A randomized trial. Am J Med 2013;126(2):141-9. PubMed
- Hankey GJ, Eikelboom JW, Yi Q, et al. Treatment with B vitamins and incidence of cancer in patients with previous stroke or transient ischemic attack: Results of a randomized placebo-controlled trial. Stroke 2012;43(6):1572-7. PubMed
- Hoyer-Kuhn H, Kohbrok S, Volland R, Franklin J, Hero B, Beck BB, Hoppe B. Vitamin B6 in primary hyperoxaluria I: first prospective trial after 40 years of practice. Clin J Am Soc Nephrol. 2014 Mar;9(3):468-77. PubMed
- Mahmoud A, Tabassum S, Al Enazi S, et al. Amelioration of levetiracetam-induced behavioral side effects by pyridoxine. A randomized double blind controlled study. Pediatr Neurol 2021;119:15-21. PubMed
- Gupta M, Gallante B, Bamberger JN, et al. Prospective randomized evaluation of idiopathic hyperoxaluria treatments. J Endourol 2021;35(12):1844-1851. PubMed
- Li H, Chen M, Liang S, et al. Excessive vitamin B6 during treatment is related to poor prognosis of patients with nasopharyngeal carcinoma: A U-shaped distribution suggests low dose supplement. Clin Nutr 2021;40(4):2293-2300. PubMed
- Tanigawa J, Nabatame S, Tominaga K, et al. High-dose pyridoxine treatment for inherited glycosylphosphatidylinositol deficiency. Brain Dev 2021;43(6):680-687. PubMed
- Committee on Practice Bulletins-Obstetrics. ACOG Practice Bulletin No. 189: Nausea And Vomiting Of Pregnancy. Obstet Gynecol. 2018;131(1):e15-e30. PubMed
Quercetin 26 references
- Shoskes DA, Zeitlin SI, Shahed A, Rajfer J. Quercetin in men with category III chronic prostatitis: A preliminary prospective, double-blind, placebo-controlled trial. Urol 1999;54:960-3. PubMed
- Starvic B. Quercetin in our diet: from potent mutagen to probable anticarcinogen. Clin Biochem 1994;27:245-8. PubMed
- Ferry DR, Smith A, Malkhandi J, et al. Phase I clinical trial of the flavonoid quercetin: Pharmacokinetics and evidence for in vivo tyrosine kinase inhibition. Clin Cancer Res 1996;2:659-67..
- Obach RS. Inhibition of human cytochrome P450 enzymes by constituents of St. John's wort, an herbal preparation used in the treatment of depression. J Pharmacol Exp Ther 2000;294:88-95. DOI
- Edwards RL, Lyon T, Litwin SE, et al. Quercetin reduces blood pressure in hypertensive subjects. J Nutr 2007;137:2405-11.
- Kim KA, Park PW, Kim HK, et al. Effect of quercetin on the pharmacokinetics of rosiglitazone, a CYP2C8 substrate, in healthy subjects. J Clin Pharmacol 2005;45:941-6. PubMed
- DiCenzo R, Frerichs V, Larppanichpoonphol P, et al. Effect of quercetin on the plasma and intracellular concentrations of saquinavir in healthy adults. Pharmacotherapy 2006;26:1255-61. PubMed
- Choi JS, Choi BC, Choi KE. Effect of quercetin on the pharmacokinetics of oral cyclosporine. Am J Health Syst Pharm 2004;61:2406-9. PubMed
- Choi JS, Jo BW, Kim YC. Enhanced paclitaxel bioavailability after oral administration of paclitaxel or prodrug to rats pretreated with quercetin. Eur J Pharm Biopharm 2004;57:313-8. PubMed
- Vaclavikova R, Horsky S, Simek P, Gut I. Paclitaxel metabolism in rat and human liver microsomes is inhibited by phenolic antioxidants. Naunyn Schmiedebergs Arch Pharmacol 2003;368:200-9. PubMed
- Di Bari L, Ripoli S, Pradhan S, Salvadori P. Interactions between quercetin and warfarin for albumin binding: A new eye on food/drug interference. Chirality 2010;22:593-6. PubMed
- Lamson, D. W. and Brignall, M. S. Antioxidants and cancer, part 3: quercetin. Altern.Med.Rev. 2000;5(3):196-208.
- Duan KM, Wang SY, Ouyang W, Mao YM, Yang LJ. Effect of quercetin on CYP3A activity in Chinese healthy participants. J Clin Pharmacol 2012;52(6):940-6. PubMed
- Wang SY, Duan KM, Li Y, et al. Effect of quercetin on P-glycoprotein transport ability in Chinese healthy subjects. Eur J Clin Nutr 2013;67(4):390-4. PubMed
- Nguyen MA, Staubach P, Wolffram S, Langguth P. Effect of single-dose and short-term administration of quercetin on the pharmacokinetics of talinolol in humans - Implications for the evaluation of transporter-mediated flavonoid-drug interactions. Eur J Pha PubMed
- Wu LX, Guo CX, Chen WQ, et al. Inhibition of the organic anion-transporting polypeptide 1B1 by quercetin: an in vitro and in vivo assessment. Br J Clin Pharmacol 2012;73(5):750-7.
- Ahrens MJ, Thompson DL. Effect of emulin on blood glucose in type 2 diabetics. J Med Food. 2013;16(3):211-5. PubMed
- Larson A, Witman MA, Guo Y, et al. Acute, quercetin-induced reductions in blood pressure in hypertensive individuals are not secondary to lower plasma angiotensin-converting enzyme activity or endothelin-1: nitric oxide. Nutr Res. 2012;32(8):557-64. PubMed
- Bedada SK, Neerati P. Evaluation of the effect of quercetin treatment on CYP2C9 enzyme activity of diclofenac in healthy human volunteers. Phytother Res. 2018 Feb;32(2):305-311. doi: 10.1002/ptr.5978. PubMed
- Zhao Q, Wei J, Zhang H. Effects of quercetin on the pharmacokinetics of losartan and its metabolite EXP3174 in rats. Xenobiotica 2019;49(5):563-8. PubMed
- Bhutani P, Rajanna PK, Paul AT. Impact of quercetin on pharmacokinetics of quetiapine: insights from in-vivo studies in wistar rats. Xenobiotica. 2020:1-7.
- Li C, Wang X, Bi Y, et al. Potent Inhibitors of Organic Anion Transporters 1 and 3 From Natural Compounds and Their Protective Effect on Aristolochic Acid Nephropathy. Toxicol Sci. 2020;175(2):279-291. PubMed
- Ni Y, Duan Z, Zhou D, et al. Identification of Structural Features for the Inhibition of OAT3-Mediated Uptake of Enalaprilat by Selected Drugs and Flavonoids. Front Pharmacol. 2020;11:802. PubMed
- Song YK, Yoon JH, Woo JK, et al. Quercetin is a flavonoid breast cancer resistance protein inhibitor with an impact on the oral pharmacokinetics of sulfasalazine in rats. Pharmaceutics 2020;12(5):397. PubMed
- Ahmad E, Jahangir M, Ismail MA, et al. Influence of quercetin pretreatment on pharmacokinetics of warfarin in rats. Curr Drug Saf 2022. PubMed
- Nambiar A, Kellogg D 3rd, Justice J, et al. Senolytics dasatinib and quercetin in idiopathic pulmonary fibrosis: results of a phase I, single-blind, single-center, randomized, placebo-controlled pilot trial on feasibility and tolerability. EBioMedicine 20 PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC