
Inflameric Ingredients & Drug Interactions
What is this page for?
First and foremost: checking Inflameric against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Inflameric is a dietary supplement by OL Olympian Labs with 16 active ingredients. Its ingredients are commonly taken for common cold and immune support, antioxidant support, skin health and collagen formation.Based on those ingredients, 1,542 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Green Tea extract, Turmeric root extract, Cat's Claw. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Inflameric by OL Olympian Labs
Ask about any prescription or over-the-counter medication and we check it for interactions with Inflameric by OL Olympian Labs — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Inflameric by OL Olympian Labs
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Low disclosure
Inflameric contains 16 ingredients, most of which are digestive enzymes and botanical extracts. The active ingredients include vitamin C, zinc, the digestive enzymes protease, lipase, and amylase, copper, and a series of herbal extracts: cat's claw, gymnema sylvestre, green tea, turmeric root, devil's claw, boswellia serrata, and yucca.
The product also contains MSM and proprietary enzyme and herbal blends whose exact component amounts aren't specified on the label. The capsules themselves are vegetarian, and the inactive ingredients include rice flour, microcrystalline cellulose, silicon dioxide, and ascorbyl palmitate.
Does it work?
Strong evidence
The evidence for Inflameric's ingredients varies widely. Vitamin C is effective for preventing deficiency and possibly effective for anemia and certain other conditions.
Zinc is effective for zinc deficiency and possibly effective for acne and age-related vision loss, though evidence for diabetes is limited. For the botanical components, turmeric is possibly effective for depression and digestive upset, while devil's claw is possibly effective for back pain and osteoarthritis.
Green tea has possibly effective evidence for certain cancers. For gymnema, boswellia serrata, cat's claw, and yucca, the evidence we hold shows insufficient reliable data to establish effectiveness for the conditions they're used for.
Protease, lipase, and the other digestive enzymes lack established effectiveness ratings in our data.
How safe is it?
Well-documented data
Vitamin C is generally well tolerated at normal doses, though very high doses can cause stomach upset, heartburn, and kidney stones in those prone to them. Zinc is well tolerated below 40 mg daily but can cause nausea, diarrhea, and a metallic taste, especially at higher doses.
Protease and lipase are generally well tolerated, though protease may rarely cause allergic reactions in sensitive individuals. Copper is safe in amounts found in food and standard supplements.
Cat's claw, gymnema, turmeric, devil's claw, and boswellia serrata are generally well tolerated short-term but carry limited long-term safety data. For pregnancy and breastfeeding: vitamin C at normal amounts is likely safe, though high-dose supplements should be avoided.
Zinc is likely safe in pregnancy but possibly unsafe at high doses. Safety data for cat's claw in pregnancy advises against use.
Gymnema, devil's claw, turmeric, and boswellia serrata all lack sufficient safety data in pregnancy—talk with your doctor or pharmacist before using if you're pregnant or breastfeeding. Protease, lipase, and yucca have no pregnancy/lactation data on file.
Meds to double-check
Major interaction found
Before taking Inflameric, double-check these medication types with your doctor or pharmacist, starting with the most serious. Green tea extract may dramatically reduce the effectiveness of nadolol and atorvastatin, and may cause dangerous interactions with ephedrine.
Vitamin C, at high doses, may reduce warfarin effectiveness and increase estrogen levels from birth control or hormone therapy. Zinc may reduce absorption of several antibiotics and some HIV drugs.
Gymnema may increase the risk of low blood sugar if you take diabetes medications. Cat's claw may affect blood pressure control and blood thinners.
Turmeric may interfere with immunosuppressants and certain chemotherapy drugs. Devil's claw and boswellia serrata may increase levels of drugs your liver breaks down.
Copper with birth control pills may theoretically raise copper levels. If you take any of these medications, run them through the checker below before adding this product.
The bottom line
Scorecard at a glanceFormula with limited ingredient disclosure with strong clinical evidence behind its ingredients' uses. Major medication interactions have been identified, and safety information is well characterized.
Inflameric is a multi-ingredient supplement intended to support digestive and inflammatory processes through enzymes and botanicals. If you take any prescription medications—especially blood pressure drugs, blood thinners, diabetes medications, birth control, or drugs processed by your liver—check each one against the medication interaction tool on this page before you start.
Pregnant or breastfeeding people should talk with their doctor or pharmacist about whether this product is right for them, given the limited safety data on several of its herbal ingredients.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 12 of 16 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jan 22, 2022.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Inflameric, straight from the product label.
| Brand | OL Olympian Labs |
|---|---|
| Barcode (UPC) | 710013030191 |
| Net contents | 90 Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Jan 22, 2022 |
| DSLD ID | 259776 |
| Product type | Other Combinations |
| Supplement form | Capsule |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), No Allergies, Dairy Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for Inflameric by OL Olympian Labs, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Vitamin C | 60 mg | 100% |
| Zinc | 5 mg | 33% |
| Amylase | 0 NP | -- |
| Protease | 0 NP | -- |
| Lipase | 0 NP | -- |
| Cellulase | 0 NP | -- |
| MSM | 500 mg | -- |
| Proprietary Herbal Blend | 209.75 mg | -- |
| Copper | 1 mg | 50% |
| Cat's Claw | 0 NP | -- |
| Proprietary Enzyme Blend | 100 mg | -- |
| Gymnema sylvestre extract | 0 NP | -- |
| Green Tea extract | 50 mg | -- |
| Turmeric root extract | 75 mg | -- |
| Devil's Claw | 0 NP | -- |
| Boswellia serrata | 600 mg | -- |
| Yucca | 0 NP | -- |
| Sea Cucumber | 0 NP | -- |
Other ingredients: Vegetarian Capsule, Rice Flour, Microcrystalline Cellulose, Silicon Dioxide, Ascorbyl Palmitate
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formulation
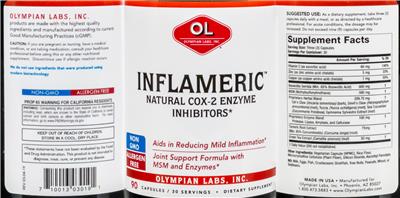
Olympian Labs, Inc. products are made with the highest quality ingredients and manufactured according to current Good Manufacturing Practices (cGMP).
We do not use ingredients that were produced using modern biotechnology Non-GMO
Allergen free
Natural COX-2 enzyme inhibitors Aids in reducing mild inflammation
No: Milk, eggs, fish, crustaceans shellfish, tree nuts, peanuts, wheat, or soybeans.
Made in USA
Precautions
Caution: If you are pregnant or nursing, have a medical condition, or are taking medication, consult your healthcare professional before using this or any other nutritional supplement.
Discontinue use if allergic reaction occurs.
Prop 65 Warning for California Residents Warning: Consuming this product can expose you to chemicals, including lead, which are known to the State of California to cause cancer and birth defects or other reproductive harm. For more information, go to www.P65Warnings.ca.gov.
Keep out of reach of children.
Storage
Store in a cool, dry place.
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure, or prevent any disease.
Formula
Joint support formula with MSM and enzymes
FDA Statement of Identity
Dietary Supplement
Suggested/Recommended/Usage/Directions
Suggested use: As a dietary supplement, take three (3) capsules daily with a meal, or as directed by a healthcare professional. For acute conditions, the dosage may be increased. Do not exceed nine (9) capsules per day.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Inflameric by OL Olympian Labs label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Inflameric by OL Olympian Labs
These are the 16 active ingredients this product is made of. Select any to open its full monograph.
Serving size3 Capsule(s) Dosage formCapsule Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Vitamin C
Interacts with207 drugs
Vitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for im...
Vitamin C monograph & interactionsZinc
Interacts with67 drugs
Zinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but suppleme...
Zinc monograph & interactionsMSM
Proprietary Herbal Blend
- › Cat's Claw
- › Gymnema sylvestre extract
- › Devil's Claw
- › Yucca
- › Sea Cucumber
Copper
Interacts with31 drugs
Copper is an essential trace mineral your body needs in small amounts for making red blood cells, supporting nerves and bones, and helping enzymes wor...
Copper monograph & interactionsGreen Tea extract
Interacts with1,293 drugs
Green tea is a popular beverage rich in antioxidants called catechins, and drinking it in normal amounts is considered safe for most people. Concentra...
Green Tea extract monograph & interactionsTurmeric root extract
Interacts with1,133 drugs
Turmeric is a popular spice whose main active compounds, curcuminoids, are studied mostly for inflammation and joint pain. Some research is promising,...
Turmeric root extract monograph & interactionsBoswellia serrata
Interacts with952 drugs
Boswellia serrata is a tree resin used in traditional medicine, mainly for joint pain and inflammation. Some studies suggest it may help with osteoart...
Boswellia serrata monograph & interactionsOther (inactive) ingredients: Vegetarian Capsule, Rice Flour, Microcrystalline Cellulose, Silicon Dioxide, Ascorbyl Palmitate. These complete the product’s ingredient list but are not active constituents.
Inflameric by OL Olympian Labs Drug Interactions
HelloPharmacist Interaction Report
Inflameric by OL Olympian Labs contains several ingredients with documented interactions with medications.
Through its vitamin C, zinc, copper, cat's claw, gymnema, green tea extract, turmeric, devil's claw, and boswellia serrata content, this product interacts with a number of drug types. The most serious interactions are Major in severity: green tea extract can reduce the effectiveness of nadolol (a blood pressure medication) by approximately 85%, and it may also increase the risk of dangerous stimulant effects when combined with ephedrine, or reduce the effectiveness of atorvastatin (a cholesterol medication) by about 24%.
Read the full breakdown — every affected drug type, severity by severity
Vitamin C carries Moderate interactions with estrogens (including birth control and hormone therapy), blood thinners like warfarin, chemotherapy drugs, and several other medications. Zinc may reduce absorption of certain antibiotics (quinolones, tetracyclines, cephalexin) and some HIV medications.
Cat's claw theoretically may affect blood pressure medications, blood thinners, and drugs broken down by your liver. Gymnema may increase the risk of low blood sugar if you take diabetes medications.
Turmeric interacts with several chemotherapy drugs, immunosuppressants, and other medications processed by your liver.
Devil's claw and boswellia serrata may increase levels of drugs your liver metabolizes through cytochrome P450 enzymes. Copper carries Minor interactions with birth control pills.
We could not check amylase, cellulase, MSM, sea cucumber, or the specific herbal components within the proprietary blends, as interaction data is not held for those ingredients.
Altogether, these interactions span 1,543 individual medications. Use the medication checker below with your specific prescriptions before starting this product, and talk with your doctor or pharmacist about any concerns.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Inflameric?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Inflameric interact with 1,542 drugs. Click any drug to see the details.
9 of the 16 ingredients in Inflameric interact with drugs. Each result below shows which ingredient is responsible. Green Tea extract Turmeric root extract Cat's Claw Boswellia serrata Gymnema sylvestre extract Devil's Claw Vitamin C Zinc Copper
Aminophylline, Amobarbital, EphedrineAmesec
How Aminophylline, Amobarbital, Ephedrine interacts with Inflameric — through 1 ingredient. Tap an ingredient for the detail:
Green Tea ExtractStimulant Drugs, Ephedrine Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Extract + Aminophylline, Amobarbital, Ephedrine interactionAtorvastatinAtorvaliq
How Atorvastatin interacts with Inflameric — through 6 ingredients. Tap an ingredient for the detail:
Green Tea ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Atorvastatin (lipitor) +2 Major
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Extract + Atorvastatin interactionBoswellia SerrataCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Boswellia Serrata + Atorvastatin interactionDevil's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, devil's claw might increase levels of drugs metabolized by CYP3A4.
Read the full Devil's Claw + Atorvastatin interactionCat's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, cat's claw might increase or decrease the levels and effects of drugs metabolized by CYP3A4.
Read the full Cat's Claw + Atorvastatin interactionTurmeric Root ExtractHepatotoxic Drugs, Organic Anion-transporting Polypeptide Substrates (oatp) +1 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Atorvastatin interactionGymnema Sylvestre ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre Extract + Atorvastatin interactionAtorvastatin CalciumLipitor
How Atorvastatin Calcium interacts with Inflameric — through 6 ingredients. Tap an ingredient for the detail:
Green Tea ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +2 Major
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract + Atorvastatin Calcium interactionTurmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Atorvastatin Calcium interactionCat's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, cat's claw might increase or decrease the levels and effects of drugs metabolized by CYP3A4.
Read the full Cat's Claw + Atorvastatin Calcium interactionBoswellia SerrataCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Boswellia Serrata + Atorvastatin Calcium interactionDevil's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, devil's claw might increase levels of drugs metabolized by CYP3A4.
Read the full Devil's Claw + Atorvastatin Calcium interactionGymnema Sylvestre ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre Extract + Atorvastatin Calcium interactionBendroflumethiazide, NadololCorzide
How Bendroflumethiazide, Nadolol interacts with Inflameric — through 2 ingredients. Tap an ingredient for the detail:
Green Tea ExtractDiuretic Drugs, Nadolol (corgard) Major
Interaction Summary
Theoretically, using green tea with diuretic drugs might increase the risk of hypokalemia.
Read the full Green Tea Extract + Bendroflumethiazide, Nadolol interactionCat's ClawAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking cat's claw with antihypertensive drugs might increase the risk of hypotension.
Read the full Cat's Claw + Bendroflumethiazide, Nadolol interactionCarbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine TannateQuadratuss, Ry Tuss, Rynatuss, Tri Tannate Plus
How Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interacts with Inflameric — through 6 ingredients. Tap an ingredient for the detail:
Green Tea ExtractEphedrine, Stimulant Drugs +1 Major
Interaction Summary
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Read the full Green Tea Extract + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionDevil's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, devil's claw might increase levels of drugs metabolized by CYP3A4.
Read the full Devil's Claw + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionTurmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionCat's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, cat's claw might increase or decrease the levels and effects of drugs metabolized by CYP3A4.
Read the full Cat's Claw + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionBoswellia SerrataCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Boswellia Serrata + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionGymnema Sylvestre ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre Extract + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionDyphylline, Ephedrine, Guaifenesin, PhenobarbitalLufyllin-EPG
How Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interacts with Inflameric — through 1 ingredient. Tap an ingredient for the detail:
Green Tea ExtractStimulant Drugs, Phenobarbital (luminal) +1 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Extract + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionEphedrine, Guaifenesin (otc Drug)Ephedrine Formula 400, Ephedrine Plus Tabs
How Ephedrine, Guaifenesin (otc Drug) interacts with Inflameric — through 1 ingredient. Tap an ingredient for the detail:
Green Tea ExtractStimulant Drugs, Ephedrine Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Extract + Ephedrine, Guaifenesin (otc Drug) interactionEphedrine, Guaifenesin, Phenobarbital, TheophyllineMudrane GG
How Ephedrine, Guaifenesin, Phenobarbital, Theophylline interacts with Inflameric — through 4 ingredients. Tap an ingredient for the detail:
Green Tea ExtractPhenobarbital (luminal), Ephedrine +2 Major
Interaction Summary
Theoretically, green tea might reduce the effects of phenobarbital and increase the risk for convulsions.
Read the full Green Tea Extract + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionGymnema Sylvestre ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP1A2.
Read the full Gymnema Sylvestre Extract + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionBoswellia SerrataCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP1A2 substrates.
Read the full Boswellia Serrata + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionTurmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionEphedrine, Hydroxyzine, TheophyllineAmi Rax, Marax
How Ephedrine, Hydroxyzine, Theophylline interacts with Inflameric — through 4 ingredients. Tap an ingredient for the detail:
Green Tea ExtractStimulant Drugs, Theophylline +1 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Extract + Ephedrine, Hydroxyzine, Theophylline interactionBoswellia SerrataCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP1A2 substrates.
Read the full Boswellia Serrata + Ephedrine, Hydroxyzine, Theophylline interactionGymnema Sylvestre ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP1A2.
Read the full Gymnema Sylvestre Extract + Ephedrine, Hydroxyzine, Theophylline interactionTurmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Ephedrine, Hydroxyzine, Theophylline interactionEphedrine, Phenobarbital, Potassium Iodide, TheophyllineMudrane, Quadrinal
How Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interacts with Inflameric — through 1 ingredient. Tap an ingredient for the detail:
Green Tea ExtractPhenobarbital (luminal), Ephedrine +2 Major
Interaction Summary
Theoretically, green tea might reduce the effects of phenobarbital and increase the risk for convulsions.
Read the full Green Tea Extract + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionEphedrine, Phenobarbital, TheophyllineTedral
How Ephedrine, Phenobarbital, Theophylline interacts with Inflameric — through 1 ingredient. Tap an ingredient for the detail:
Green Tea ExtractStimulant Drugs, Theophylline +2 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Extract + Ephedrine, Phenobarbital, Theophylline interactionEzetimibe, AtorvastatinLiptruzet
How Ezetimibe, Atorvastatin interacts with Inflameric — through 6 ingredients. Tap an ingredient for the detail:
Green Tea ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +2 Major
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract + Ezetimibe, Atorvastatin interactionTurmeric Root ExtractOrganic Anion-transporting Polypeptide Substrates (oatp), Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, turmeric might increase blood levels of OATP4C1 substrates.
Read the full Turmeric Root Extract + Ezetimibe, Atorvastatin interactionBoswellia SerrataCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Boswellia Serrata + Ezetimibe, Atorvastatin interactionCat's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, cat's claw might increase or decrease the levels and effects of drugs metabolized by CYP3A4.
Read the full Cat's Claw + Ezetimibe, Atorvastatin interactionDevil's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, devil's claw might increase levels of drugs metabolized by CYP3A4.
Read the full Devil's Claw + Ezetimibe, Atorvastatin interactionGymnema Sylvestre ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre Extract + Ezetimibe, Atorvastatin interactionNadololCorgard, Nadolol
How Nadolol interacts with Inflameric — through 2 ingredients. Tap an ingredient for the detail:
Green Tea ExtractNadolol (corgard) Major
Interaction Summary
Green tea seems to reduce the levels and clinical effects of nadolol.
Read the full Green Tea Extract + Nadolol interactionCat's ClawAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking cat's claw with antihypertensive drugs might increase the risk of hypotension.
Read the full Cat's Claw + Nadolol interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with Inflameric — through 4 ingredients. Tap an ingredient for the detail:
Green Tea ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract + 6-mercaptopurine interactionTurmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + 6-mercaptopurine interactionCat's ClawImmunosuppressants Moderate
Interaction Summary
Theoretically, cat's claw might interfere with immunosuppressive therapy.
Read the full Cat's Claw + 6-mercaptopurine interactionBoswellia SerrataImmunosuppressants Moderate
Interaction Summary
Theoretically, Boswellia serrata might alter the effects of immunosuppressive drugs.
Read the full Boswellia Serrata + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with Inflameric — through 6 ingredients. Tap an ingredient for the detail:
Boswellia SerrataCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Boswellia Serrata + Ado-trastuzumab Emtansine interactionDevil's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, devil's claw might increase levels of drugs metabolized by CYP3A4.
Read the full Devil's Claw + Ado-trastuzumab Emtansine interactionCat's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, cat's claw might increase or decrease the levels and effects of drugs metabolized by CYP3A4.
Read the full Cat's Claw + Ado-trastuzumab Emtansine interactionTurmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Ado-trastuzumab Emtansine interactionGreen Tea ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Extract + Ado-trastuzumab Emtansine interactionGymnema Sylvestre ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre Extract + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with Inflameric — through 2 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Abacavir Sulfate, Dolutegravir, Lamivudine interactionGreen Tea ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with Inflameric — through 2 ingredients. Tap an ingredient for the detail:
Green Tea ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract + Abacavir, Lamivudine interactionTurmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Abacavir, Lamivudine interactionAbametapirXeglyze
How Abametapir interacts with Inflameric — through 1 ingredient. Tap an ingredient for the detail:
Green Tea ExtractCytochrome P450 1a2 (cyp1a2) Inhibitors Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Read the full Green Tea Extract + Abametapir interactionAbciximabReoPro
How Abciximab interacts with Inflameric — through 3 ingredients. Tap an ingredient for the detail:
Cat's ClawAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, cat's claw may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Cat's Claw + Abciximab interactionGreen Tea ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea Extract + Abciximab interactionTurmeric Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Root Extract + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with Inflameric — through 6 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Abemaciclib interactionCat's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, cat's claw might increase or decrease the levels and effects of drugs metabolized by CYP3A4.
Read the full Cat's Claw + Abemaciclib interactionBoswellia SerrataCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Boswellia Serrata + Abemaciclib interactionDevil's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, devil's claw might increase levels of drugs metabolized by CYP3A4.
Read the full Devil's Claw + Abemaciclib interactionGreen Tea ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Extract + Abemaciclib interactionGymnema Sylvestre ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre Extract + Abemaciclib interactionAbiraterone
How Abiraterone interacts with Inflameric — through 6 ingredients. Tap an ingredient for the detail:
Devil's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, devil's claw might increase levels of drugs metabolized by CYP3A4.
Read the full Devil's Claw + Abiraterone interactionGreen Tea ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Inhibitors +1 Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract + Abiraterone interactionTurmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Abiraterone interactionCat's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, cat's claw might increase or decrease the levels and effects of drugs metabolized by CYP3A4.
Read the full Cat's Claw + Abiraterone interactionBoswellia SerrataCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Boswellia Serrata + Abiraterone interactionGymnema Sylvestre ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre Extract + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with Inflameric — through 6 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Abiraterone Acetate interactionDevil's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, devil's claw might increase levels of drugs metabolized by CYP3A4.
Read the full Devil's Claw + Abiraterone Acetate interactionGreen Tea ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract + Abiraterone Acetate interactionBoswellia SerrataCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Boswellia Serrata + Abiraterone Acetate interactionCat's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, cat's claw might increase or decrease the levels and effects of drugs metabolized by CYP3A4.
Read the full Cat's Claw + Abiraterone Acetate interactionGymnema Sylvestre ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre Extract + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with Inflameric — through 6 ingredients. Tap an ingredient for the detail:
Cat's ClawAnticoagulant/antiplatelet Drugs, Immunosuppressants Moderate
Interaction Summary
Theoretically, cat's claw may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Cat's Claw + Abrocitinib interactionGreen Tea ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea Extract + Abrocitinib interactionDevil's ClawCytochrome P450 2c19 (cyp2c19) Substrates, Cytochrome P450 2c9 (cyp2c9) Substrates Moderate
Interaction Summary
Theoretically, devil's claw might increase levels of drugs metabolized by CYP2C19.
Read the full Devil's Claw + Abrocitinib interactionTurmeric Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Root Extract + Abrocitinib interactionGymnema Sylvestre ExtractCytochrome P450 2c9 (cyp2c9) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase or decrease levels of drugs metabolized by CYP2C9.
Read the full Gymnema Sylvestre Extract + Abrocitinib interactionBoswellia SerrataCytochrome P450 2c9 (cyp2c9) Substrates, Immunosuppressants +1 Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP2C9 substrates.
Read the full Boswellia Serrata + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with Inflameric — through 6 ingredients. Tap an ingredient for the detail:
Boswellia SerrataCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Boswellia Serrata + Acalabrutinib interactionGreen Tea ExtractP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Green tea might increase the levels and adverse effects of P-glycoprotein (P-gp) substrates.
Read the full Green Tea Extract + Acalabrutinib interactionDevil's ClawCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, devil's claw might increase levels of drugs metabolized by CYP3A4.
Read the full Devil's Claw + Acalabrutinib interactionCat's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, cat's claw might increase or decrease the levels and effects of drugs metabolized by CYP3A4.
Read the full Cat's Claw + Acalabrutinib interactionTurmeric Root ExtractCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
Read the full Turmeric Root Extract + Acalabrutinib interactionGymnema Sylvestre ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
Read the full Gymnema Sylvestre Extract + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Inflameric — through 3 ingredients. Tap an ingredient for the detail:
Gymnema Sylvestre ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking gymnema with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Gymnema Sylvestre Extract + Acarbose interactionGreen Tea ExtractHepatotoxic Drugs, Antidiabetes Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract + Acarbose interactionTurmeric Root ExtractAntidiabetes Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking turmeric with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Turmeric Root Extract + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Inflameric — through 3 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acebutolol interactionGreen Tea ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract + Acebutolol interactionCat's ClawAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking cat's claw with antihypertensive drugs might increase the risk of hypotension.
Read the full Cat's Claw + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Inflameric — through 3 ingredients. Tap an ingredient for the detail:
Cat's ClawAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, cat's claw may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Cat's Claw + Acenocoumarol interactionTurmeric Root ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Turmeric Root Extract + Acenocoumarol interactionGreen Tea ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea Extract + Acenocoumarol interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with Inflameric — through 5 ingredients. Tap an ingredient for the detail:
Boswellia SerrataCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP1A2 substrates.
Read the full Boswellia Serrata + Acetaminophen interactionGreen Tea ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract + Acetaminophen interactionGymnema Sylvestre ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP1A2.
Read the full Gymnema Sylvestre Extract + Acetaminophen interactionTurmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with Inflameric — through 6 ingredients. Tap an ingredient for the detail:
Turmeric Root ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2.
Read the full Turmeric Root Extract + Acetaminophen, Aspirin interactionCat's ClawAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, cat's claw may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Cat's Claw + Acetaminophen, Aspirin interactionGreen Tea ExtractHepatotoxic Drugs, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Extract + Acetaminophen, Aspirin interactionBoswellia SerrataCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP1A2 substrates.
Read the full Boswellia Serrata + Acetaminophen, Aspirin interactionGymnema Sylvestre ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP1A2.
Read the full Gymnema Sylvestre Extract + Acetaminophen, Aspirin interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with Inflameric — through 7 ingredients. Tap an ingredient for the detail:
Green Tea ExtractAnticoagulant/antiplatelet Drugs, Stimulant Drugs +2 Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea Extract + Acetaminophen, Aspirin, Caffeine interactionDevil's ClawCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, devil's claw might increase levels of drugs metabolized by CYP3A4.
Read the full Devil's Claw + Acetaminophen, Aspirin, Caffeine interactionCat's ClawAnticoagulant/antiplatelet Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, cat's claw may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Cat's Claw + Acetaminophen, Aspirin, Caffeine interactionTurmeric Root ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +2 Moderate
Interaction Summary
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
Read the full Turmeric Root Extract + Acetaminophen, Aspirin, Caffeine interactionGymnema Sylvestre ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, gymnema might increase levels of drugs metabolized by CYP1A2.
Read the full Gymnema Sylvestre Extract + Acetaminophen, Aspirin, Caffeine interactionBoswellia SerrataCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP1A2 substrates.
Read the full Boswellia Serrata + Acetaminophen, Aspirin, Caffeine interactionVitamin CAspirin, Acetaminophen (tylenol, Others) Minor
Interaction Summary
Acidification of the urine by vitamin C might increase aspirin levels.
Read the full Vitamin C + Acetaminophen, Aspirin, Caffeine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Inflameric with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Green Tea extract
Atorvastatin (Lipitor)
Green tea extract seems to reduce the levels and clinical effects of atorvastatin.
In healthy humans, taking green tea extract 300 mg or 600 mg along with atorvastatin reduces plasma levels of atorvastatin by approximately 24%. The elimination of atorvastatin is not affected. Atorvastatin is a substrate of organic anion-transporting polypeptides (OATPs). Research shows that two of the major catechins found in green tea, epicatechin gallate (ECG) and epigallocatechin gallate (EGCG), inhibit OATPs. Some OATPs are expressed in the small intestine and are responsible for the uptake of drugs and other compounds, which may have resulted in reduced plasma levels of atorvastatin. It is not clear if drinking green tea alters the absorption of atorvastatin.
Ephedrine
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Green tea contains caffeine. There is evidence that using ephedrine with caffeine might increase the risk of serious life-threatening or debilitating adverse effects such as hypertension, myocardial infarction, stroke, seizures, and death.
Nadolol (Corgard)
Green tea seems to reduce the levels and clinical effects of nadolol.
Preliminary clinical research shows that green tea consumption reduces plasma concentrations of nadolol. Compared to a control group, both peak levels and total drug exposure (AUC) of nadolol were reduced by approximately 85% in subjects who drank green tea daily for two weeks. Drinking green tea with nadolol also significantly reduced nadolol's systolic blood pressure lowering effect. Other clinical research shows that a single dose of green tea can affect plasma nadolol levels for at least one hour. Green tea catechins have been shown to inhibit organic anion transporting polypeptides (OATP), one of which, OATP1A2, is involved in the uptake of nadolol in the intestine The interaction is thought to be due primarily to the epigallocatechin gallate (EGCG) content of green tea.
5-Fluorouracil
Theoretically, high doses of green tea might increase the effects and side effects of 5-fluorouracil.
Animal research shows that taking green tea in amounts equivalent to about 6 cups daily in humans for 4 weeks prior to receiving a single injection of 5-fluorouracil increases the maximum plasma levels of 5-fluorouracil by about 2.5-fold and the area under the curve by 425%.
Adenosine (Adenocard)
Theoretically, green tea might decrease the vasodilatory effects of adenosine and interfere with its use prior to stress testing.
Green tea contains caffeine. Caffeine is a competitive inhibitor of adenosine at the cellular level. However, caffeine doesn't seem to affect supplemental adenosine because high interstitial levels of adenosine overcome the antagonistic effects of caffeine. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. However, methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Anticoagulant/Antiplatelet Drugs
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Conflicting reports exist regarding the effect of green tea on bleeding risk when used with anticoagulant or antiplatelet drugs; however, most evidence suggests that drinking green tea in moderate amounts is unlikely to cause a significant interaction. Green tea contains small amounts of vitamin K, approximately 7 mcg per cup. Some case reports have associated the antagonism of warfarin with the vitamin K content of green tea. However, these reports are rare, and very large doses of green tea (about 8-16 cups daily) appear to be needed to cause these effects. Furthermore, the catechins and caffeine in green tea are reported to have antiplatelet activity.
Beta-Adrenergic Agonists
Green tea contains caffeine. Theoretically, concomitant use of large amounts of caffeine might increase cardiac inotropic effects of beta-agonists.
Bortezomib (Velcade)
Theoretically, green tea might interfere with the effects of bortezomib.
In vitro research shows that green tea polyphenols, such as epigallocatechin gallate (EGCG), interact with bortezomib and block its proteasome inhibitory action. This prevents the induction of cell death in multiple myeloma or glioblastoma cancer cell lines. Advise patients taking bortezomib, not to take green tea.
Carbamazepine (Tegretol)
Theoretically, green tea might reduce the effects of carbamazepine and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that taking caffeine can lower the anticonvulsant effects of carbamazepine and can induce seizures when taken in doses above 400 mg/kg. Human research has shown that taking caffeine 300 mg in three divided doses along with carbamazepine 200 mg reduces the bioavailability of carbamazepine by 32% and prolongs the plasma half-life of carbamazepine 2-fold in healthy individuals.
Celiprolol (Celicard)
Theoretically, green tea might reduce the levels and clinical effects of celiprolol.
In a small human study, taking green tea daily for 4 days appears to decrease blood and urine levels of celiprolol by at least 98%. This interaction is possibly due to the inhibition of organic anion transporting polypeptide (OATP). Green tea catechins have been shown to inhibit organic anion transporting polypeptides (OATP), one of which, OATP1A2, is found in the intestine The interaction is thought to be due primarily to the epigallocatechin gallate (EGCG) content of green tea.
Cimetidine (Tagamet)
Theoretically, concomitant use might increase the effects and adverse effects of caffeine in green tea.
Green tea contains caffeine. Cimetidine can reduce caffeine clearance by 31% to 42%.
Clozapine (Clozaril)
Theoretically, green tea might increase the levels and adverse effects of clozapine and acutely exacerbate psychotic symptoms.
Animal research suggests that, although green tea extract does not affect the elimination of clozapine, it delays the time to reach peak concentration and reduces the peak plasma levels. Also, concomitant administration of green tea and clozapine might theoretically cause acute exacerbation of psychotic symptoms due to the caffeine in green tea. Caffeine can increase the effects and toxicity of clozapine. Caffeine doses of 400-1000 mg daily inhibit clozapine metabolism. Clozapine is metabolized by cytochrome P450 1A2 (CYP1A2). Researchers speculate that caffeine might inhibit CYP1A2. However, there is no reliable evidence that caffeine affects CYP1A2. There is also speculation that genetic factors might make some patients be more sensitive to the interaction between clozapine and caffeine.
Contraceptive Drugs
Theoretically, concomitant use might increase the effects and adverse effects of caffeine found in green tea.
Green tea contains caffeine. Oral contraceptives can decrease caffeine clearance by 40% to 65%.
Cytochrome P450 1A2 (Cyp1A2) Inhibitors
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Caffeine is metabolized by cytochrome P450 1A2 (CYP1A2),. Theoretically, drugs that inhibit CYP1A2 may decrease the clearance rate of caffeine from green tea and increase caffeine levels.
Dipyridamole (Persantine)
Theoretically, green tea might decrease the vasodilatory effects of dipyridamole and interfere with its use prior to stress testing.
Green tea contains caffeine. Caffeine might inhibit dipyridamole-induced vasodilation. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. Methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Disulfiram (Antabuse)
Theoretically, disulfiram might increase the risk of adverse effects from caffeine.
In human research, disulfiram decreases the clearance and increases the half-life of caffeine.
Diuretic Drugs
Theoretically, using green tea with diuretic drugs might increase the risk of hypokalemia.
Green tea contains caffeine. In excessive amounts, caffeine can reduce potassium levels due to stimulation of the sodium-potassium pump. Diuretics can also cause lower potassium levels.
Estrogens
Theoretically, estrogens might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Estrogen inhibits caffeine metabolism.
Ethosuximide (Zarontin)
Theoretically, green tea might reduce the effects of ethosuximide and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that caffeine 92.4 mg/kg can decrease the anticonvulsant activity of ethosuximide. However, this effect has not been reported in humans.
Felbamate (Felbatol)
Theoretically, green tea might reduce the effects of felbamate and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that a high dose of caffeine 161.7 mg/kg can decreases the anticonvulsant activity of felbamate. However, this effect has not been reported in humans.
Fexofenadine (Allegra)
Green tea can decrease blood levels of fexofenadine.
Clinical research shows that green tea can significantly decrease blood levels and excretion of fexofenadine. Taking green tea extract with a dose of fexofenadine decreased bioavailability of fexofenadine by about 30%. In vitro, green tea inhibits the cellular accumulation of fexofenadine by inhibiting the organic anion transporting polypeptide (OATP) drug transporter. Research shows that two of the major catechins found in green tea, epicatechin gallate (ECG) and epigallocatechin gallate (EGCG), inhibit OATPs, specifically OATP1A2, OATP1B1, and OATP2B1. In addition, green tea has been shown to reduce the absorption of some drugs that are OATP substrates.
Flutamide (Eulexin)
Theoretically, green tea might increase the levels and adverse effects of flutamide.
Green tea contains caffeine. In vitro evidence suggests that caffeine can inhibit the metabolism of flutamide. Theoretically, concomitant use of caffeine and flutamide might increase serum concentrations of flutamide and increase the risk adverse effects.
Fluvoxamine (Luvox)
Theoretically, fluvoxamine might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Fluvoxamine reduces caffeine metabolism.
Hepatotoxic Drugs
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Green tea extract supplements have been linked to several cases of hepatotoxicity and might have additive hepatotoxic effects with other drugs..
Imatinib (Gleevec)
Theoretically, green tea might reduce the levels and clinical effects of imatinib.
In animal research, a single dose of green tea extract reduces the area under the curve (AUC) of imatinib by up to approximately 64% and its main metabolite N-desmethyl imatinib by up to approximately 81%. This interaction has not been shown in humans. The mechanism of action is unclear but may involve multiple pathways.
Turmeric root extract
Alkylating Agents
Turmeric has antioxidant effects. Theoretically, this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro research suggests that curcumin, a constituent of turmeric, inhibits mechlorethamine-induced apoptosis of breast cancer cells by up to 70%. Also, animal research shows that curcumin inhibits cyclophosphamide-induced tumor regression. However, some in vitro research shows that curcumin does not affect the apoptosis capacity of etoposide. Also, other laboratory research suggests that curcumin might augment the cytotoxic effects of alkylating agents. Reasons for the discrepancies may relate to the dose of curcumin and the specific chemotherapeutic agent. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effect, if any, turmeric might have on alkylating agents.
Amlodipine (Norvasc)
Taking turmeric with amlodipine may increase levels of amlodipine.
Animal research shows that giving amlodipine 1 mg/kg as a single dose following the use of turmeric extract 200 mg/kg daily for 2 weeks increases the maximum concentration and area under the curve by 53% and 56%, respectively, when compared with amlodipine alone. Additional animal research shows that taking amlodipine 1 mg/kg with a curcumin 2 mg/kg pretreatment for 10 days increases the maximum concentration and area under the curve by about 2-fold when compared with amlodipine alone.
Anticoagulant/Antiplatelet Drugs
Turmeric may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs. However, research is conflicting.
Curcumin, a constituent of turmeric, has demonstrated antiplatelet effects in vitro. Furthermore, two case reports have found that taking turmeric along with warfarin or fluindione was associated with an increased international normalized ratio (INR). However, one clinical study in healthy volunteers shows that taking curcumin 500 mg daily for 3 weeks, alone or with aspirin 100 mg, does not increase antiplatelet effects or bleeding risk. It is possible that the dose of turmeric used in this study was too low to produce a notable effect.
Antidiabetes Drugs
Theoretically, taking turmeric with antidiabetes drugs might increase the risk of hypoglycemia.
Animal research and case reports suggest that curcumin, a turmeric constituent, can reduce blood glucose levels in patients with diabetes. Furthermore, clinical research in adults with type 2 diabetes shows that taking curcumin 475 mg daily for 10 days prior to taking glyburide 5 mg decreased postprandial glucose levels for up to 24 hours when compared with glyburide alone, despite the lack of a significant pharmacokinetic interaction. Other clinical studies in patients with diabetes show that taking curcumin daily can reduce blood glucose levels when compared with placebo.
Antitumor Antibiotics
Turmeric has antioxidant effects. Theoretically, this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro and animal research shows that curcumin, a constituent of turmeric, inhibits doxorubicin-induced apoptosis of breast cancer cells by up to 65%. However, curcumin does not seem to affect the apoptosis capacity of daunorubicin. In fact, some research shows that curcumin might augment the cytotoxic effects of antitumor antibiotics, increasing their effectiveness. Reasons for the discrepancies may relate to the dose of curcumin and the chemotherapeutic agent. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effects, if any, antioxidants such as turmeric have on antitumor antibiotics.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Turmeric might increase or decrease levels of drugs metabolized by CYP3A4.
In vitro and animal research show that turmeric and its constituents curcumin and curcuminoids inhibit CYP3A4. Also, 8 case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking turmeric and cancer medications that are CYP3A4 substrates, including everolimus, ruxolitinib, ibrutinib, and palbociclib, and bortezomib. In another case report, a transplant patient presented with acute nephrotoxicity and elevated tacrolimus levels after consuming turmeric powder at a dose of 15 or more spoonfuls daily for ten days prior. It was thought that turmeric increased levels of tacrolimus due to CYP3A4 inhibition.
Conversely, other in vitro research suggests that turmeric induces CYP3A4 activity, leading to reduced levels of CYP3A4 substrates. An animal model suggests that induction of CYP3A4 occurs after daily curcumin use for 1 week. However, the induction of CYP3A4 by turmeric has not been reported in humans.
Hepatotoxic Drugs
Theoretically, turmeric might increase the risk of liver damage when taken with hepatotoxic drugs.
There is concern that turmeric might cause hepatotoxicity, especially when highly bioavailable formulations are used in high doses.
Methotrexate (Trexall, Others)
Theoretically, turmeric might have additive effects when used with hepatotoxic drugs such as methotrexate.
In one case report, a 39-year-old female taking methotrexate, turmeric, and linseed oil developed hepatotoxicity.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Theoretically, turmeric might increase blood levels of OATP4C1 substrates.
In vitro research shows that the turmeric constituent curcumin competitively inhibits OATP4C1 transport. This transporter is expressed in the kidney and facilitates the renal excretion of certain drugs. Theoretically, taking turmeric might decrease renal excretion of OATP substrates.
Sulfasalazine (Azulfidine)
Turmeric might increase the effects and adverse effects of sulfasalazine.
Clinical research shows that taking the turmeric constituent, curcumin, can increase blood levels of sulfasalazine by 3.2-fold.
Tacrolimus (Prograf)
Turmeric might increase the effects and adverse effects of tacrolimus.
In one case report, a transplant patient presented with acute nephrotoxicity and elevated tacrolimus levels of 29 ng/mL. The patient previously had tacrolimus levels within the therapeutic range at 9.7 ng/mL. Ten days prior to presenting at the emergency room the patient started consumption of turmeric powder at a dose of 15 or more spoonfuls daily. It was thought that turmeric increased levels of tacrolimus due to cytochrome P450 3A4 (CYP3A4) inhibition. In vitro and animal research show that turmeric and its constituent curcumin inhibit CYP3A4.
Talinolol
Turmeric may reduce the absorption of talinolol in some situations.
Clinical research shows that taking curcumin for 6 days decreases the bioavailability of talinolol when taken together on the seventh day. The clinical significance of this effect is unclear.
Tamoxifen (Nolvadex)
Theoretically, turmeric might reduce the levels and clinical effects of tamoxifen.
In a small clinical trial in patients with breast cancer taking tamoxifen 20-30 mg daily, adding curcumin 1200 mg plus piperine 10 mg three times daily reduces the 24-hour area under the curve of tamoxifen and the active metabolite endoxifen by 12.8% and 12.4%, respectively, as well as the maximum concentrations of tamoxifen, when compared with tamoxifen alone. However, in the absence of piperine, the area under the curve for endoxifen and the maximum concentration of tamoxifen were not significantly reduced. Effects were most pronounced in patients who were extensive cytochrome P450 (CYP) 2D6 metabolizers.
Topoisomerase I Inhibitors
Turmeric has antioxidant effects. There is some concern that this may reduce the activity of chemotherapy drugs that generate free radicals. However, research is conflicting.
In vitro research shows that curcumin, a constituent of turmeric, inhibits camptothecin-induced apoptosis of breast cancer cells by up to 71%. However, other in vitro research shows that curcumin augments the cytotoxic effects of camptothecin. Reasons for the discrepancies may relate to the dose of curcumin and the chemotherapeutic agents. Lower doses of curcumin might have antioxidant effects while higher doses might have pro-oxidant effects. More evidence is needed to determine what effect, if any, turmeric might have.
Tramadol (Ultram)
Theoretically, turmeric might increase or decrease levels of tramadol.
Animal research suggests that a single dose of curcumin, a constituent of turmeric, may increase tramadol's maximum concentration (Cmax) by inhibiting metabolism, while continued daily use for 7 days may reduce the area under the curve (AUC) due to the induction of drug-metabolizing enzymes such as cytochrome P450 3A4 (CYP3A4). However, this interaction has not been reported in humans.
Warfarin (Coumadin)
Turmeric might increase the risk of bleeding with warfarin.
One case of increased international normalized ratio (INR) has been reported for a patient taking warfarin who began taking turmeric. Prior to taking turmeric, the patient had stable INR measurements. Within a few weeks of starting turmeric supplementation, the patient's INR increased to 10. Additionally, curcumin, the active constituent in turmeric, has demonstrated antiplatelet effects in vitro, which may produce additive effects when taken with warfarin.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, turmeric might increase levels of drugs metabolized by CYP1A2. However, research is conflicting.
In vitro and animal research show that the turmeric constituent, curcumin, inhibits CYP1A2. However, other in vitro research suggests that curcumin does not significantly affect CYP1A2.
Docetaxel (Taxotere)
Theoretically, turmeric might increase blood levels of oral docetaxel.
Animal research suggests that the turmeric constituent, curcumin, enhances the oral bioavailability of docetaxel. However, the significance of this interaction is unclear, as this drug is typically administered intravenously in clinical settings.
Estrogens
Theoretically, large amounts of turmeric might interfere with hormone replacement therapy through competition for estrogen receptors.
In vitro research shows that curcumin, a constituent of turmeric, displaces the binding of estrogen to its receptors.
Glyburide (Diabeta, Others)
Theoretically, taking turmeric and glyburide in combination might increase the risk of hypoglycemia.
Clinical research shows that taking curcumin 475 mg daily for 10 days prior to taking glyburide 5 mg increases blood levels of glyburide by 12% at 2 hours after the dose in patients with type 2 diabetes. While maximal blood concentrations of glyburide were not affected, turmeric modestly decreased postprandial glucose levels for up to 24 hours when compared to glyburide alone, possibly due to the hypoglycemic effect of turmeric demonstrated in animal research.
Losartan (Cozaar)
Theoretically, turmeric might increase the effects of losartan.
Research in hypertensive rats shows that taking turmeric can increase the hypotensive effects of losartan.
Norfloxacin (Noroxin)
Theoretically, turmeric might increase the effects and adverse effects of norfloxacin.
Animal research shows that taking curcumin, a turmeric constituent, can increase blood levels of orally administered norfloxacin.
P-Glycoprotein Substrates
Theoretically, turmeric might increase the absorption of P-glycoprotein substrates.
In vitro and animal research shows that curcuminoids and other constituents found in turmeric can inhibit P-glycoprotein expression and activity.
Paclitaxel (Abraxane, Onxol)
Theoretically, turmeric might alter blood levels of paclitaxel, although any effect may not be clinically relevant.
Clinical research in adults with breast cancer receiving intravenous paclitaxel suggests that taking turmeric may modestly alter paclitaxel pharmacokinetics. Patients received paclitaxel on day 1, followed by either no treatment or turmeric 2 grams daily from days 2-22. Pharmacokinetic modeling suggests that turmeric reduces the maximum concentration and area under the curve of paclitaxel by 12.1% and 7.7%, respectively. However, these changes are not likely to be considered clinically relevant. Conversely, animal research suggests that curcumin, a constituent of turmeric, enhances the oral bioavailability of paclitaxel. However, the significance of this interaction is unclear, as this drug is typically administered intravenously in clinical settings.
Cat's Claw
Anticoagulant/Antiplatelet Drugs
Theoretically, cat's claw may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Cat's claw contains rhynchophylline and isorhynchophylline. Animal research suggests that these alkaloids can inhibit platelet aggregation. This interaction has not been reported in humans.
Antihypertensive Drugs
Theoretically, taking cat's claw with antihypertensive drugs might increase the risk of hypotension.
Cat's claw contains rhynchophylline. In vitro and animal research suggests that rhynchophylline can lower blood pressure. This interaction has not been reported in humans.
Calcium Channel Blockers
Theoretically, taking cat's claw with calcium channel blockers might increase the risk of hypotension.
Cat's claw contains various alkaloids, including rhynchophylline, isorhynchophylline, corynoxeine, and isocorynoxiene. Animal research suggests that these alkaloids can lower blood pressure by acting as calcium channel blockers. This interaction has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, cat's claw might increase or decrease the levels and effects of drugs metabolized by CYP3A4.
Cat's claw may affect the clearance of drugs metabolized by CYP3A4. In vitro research shows that cat's claw can inhibit CYP3A4 enzymes. In one case report, a patient taking cat's claw (at an unspecified dose) experienced increased serum levels of atazanavir, ritonavir, and saquinavir, all of which are CYP3A4 substrates. Levels returned to normal 15 days after discontinuation of the cat's claw supplement, suggesting inhibition of CYP3A4 by cat's claw. In contrast, animal research suggests that rhynchophylline, an alkaloid contained in cat's claw, induces CYP3A expression and accelerates the metabolism of nirmatrelvir, the active component in the nirmatrelvir/ritonavir combination product.
Immunosuppressants
Theoretically, cat's claw might interfere with immunosuppressive therapy.
In human and laboratory research, cat's claw has been shown to have immunostimulating activity. It stimulates phagocytosis and increases respiratory cellular activity and the mobility of leukocytes. Theoretically, this could interfere with the activity of immunosuppressant medications.
Nirmatrelvir/Ritonavir (Paxlovid)
Theoretically, cat's claw may decrease the levels of nirmatrelvir.
Cat's claw contains rhynchophylline. Animal research suggests that this alkaloid induces CYP3A expression, thereby accelerating the metabolism of nirmatrelvir, the active component in the nirmatrelvir/ritonavir combination product. This interaction has not been reported in humans.
Boswellia serrata
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, Boswellia serrata might increase the levels of CYP1A2 substrates.
In vitro research shows that Boswellia serrata gum resin inhibits CYP1A2 enzymes.
Cytochrome P450 2C19 (Cyp2C19) Substrates
Theoretically, Boswellia serrata might increase the levels of CYP2C19 substrates.
In vitro research shows that Boswellia serrata gum resin inhibits CYP2C19 enzymes.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, Boswellia serrata might increase the levels of CYP2C9 substrates.
In vitro research shows that Boswellia serrata gum resin inhibits CYP2C9 enzymes.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, Boswellia serrata might increase the levels of CYP2D6 substrates.
In vitro research shows that Boswellia serrata gum resin inhibits CYP2D6 enzymes.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
In vitro research shows that Boswellia serrata gum resin inhibits CYP3A4 enzymes. Other in vitro research shows that Boswellia serrata extract inhibits CYP3A4 enzymes at most concentrations, although it may modestly induce enzyme activity at low concentrations.
Immunosuppressants
Theoretically, Boswellia serrata might alter the effects of immunosuppressive drugs.
Some in vitro research suggests that Boswellia serrata extracts might inhibit mediators of autoimmune disorders such as leukotrienes and reduce production of antibodies and cell-mediated immunity. However, other in vitro research suggests that, when coupled with calcium ions, boswellic acids containing the keto group have immunostimulant properties within specific cell signaling pathways.
Gymnema sylvestre extract
Antidiabetes Drugs
Theoretically, taking gymnema with antidiabetes drugs might increase the risk of hypoglycemia.
Gymnema reduces blood glucose levels in some human and animal research. In human studies, it has been shown to enhance the blood glucose lowering effects of hypoglycemic drugs. However, other research in adults with prediabetes or metabolic syndrome suggests that gymnema does not reduce fasting levels of blood glucose. Until more is known, monitor blood glucose levels closely.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, gymnema might increase levels of drugs metabolized by CYP1A2.
Animal and in vitro research shows that gymnema can inhibit the CYP1A2 enzyme. In one animal study, oral administration of gymnema for 7 days increased the plasma concentrations of phenacetin, a CYP1A2 substrate, by about 1.4-fold and reduced the clearance of phenacetin by about 29%.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, gymnema might increase or decrease levels of drugs metabolized by CYP2C9.
Animal research shows that gymnema can induce the CYP2C9 enzyme. In one animal study, gymnema caused a 2.4-fold increase in the clearance of tolbutamide, a CYP2C9 substrate, in rats. In vitro research also shows that gymnema can inhibit CYP2C9.
Phenacetin
Theoretically, taking gymnema with phenacetin might increase the levels of phenacetin.
Animal research shows that gymnema, administered orally for 7 days, decreases the clearance of phenacetin in a dose-dependent manner by about 21% to 29% and increases plasma levels about 1.3- to 1.4-fold when compared to control.
Tolbutamide (Orinase)
Theoretically, taking gymnema with tolbutamide might the decrease levels of tolbutamide.
Animal research shows that gymnema, administered orally for 7 days, increases the clearance of tolbutamide by 2.4-fold when compared to control.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, gymnema might increase levels of drugs metabolized by CYP3A4.
One in vitro study using rat liver microsomes shows that gymnema can modestly inhibit the CYP3A4 enzyme. However, other in vitro research using human liver microsomes shows that gymnema does not affect CYP3A4 activity. Animal research also shows that gymnema does not alter the function of CYP3A4. In one study in rats, oral administration of gymnema for 7 days did not alter the clearance of amlodipine, a CYP3A4 substrate.
Devil's Claw
Cytochrome P450 2C19 (Cyp2C19) Substrates
Theoretically, devil's claw might increase levels of drugs metabolized by CYP2C19.
In vitro research shows that devil's claw might inhibit CYP2C19, although this has not been reported in humans.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, devil's claw might increase levels of drugs metabolized by CYP2C9.
In vitro research shows that devil's claw might inhibit CYP2C9, although this has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, devil's claw might increase levels of drugs metabolized by CYP3A4.
In vitro research shows that devil's claw might inhibit CYP3A4, although this has not been reported in humans.
Warfarin (Coumadin)
Theoretically, Devil's claw might increase the activity of warfarin.
In one case report, purpura occurred in a patient taking warfarin and devil's claw concurrently. This might indicate over-anticoagulation. It is unclear if this was due to Devil's claw or other contributing factors.
H2-Blockers
Theoretically, devil's claw might decrease the effectiveness of H2-blockers.
Devil's claw has been reported to increase stomach acid, which might interfere with the effects of H2-blockers.
P-Glycoprotein Substrates
Theoretically, devil's claw might increase levels of P-glycoprotein substrates.
In vitro research shows that devil's claw inhibits P-glycoprotein, which transports many drugs out of cells. This might increase intracellular levels of P-glycoprotein substrates, although it is unclear if this effect would be clinically important.
Proton Pump Inhibitors (Ppis)
Theoretically, devil's claw might decrease the effectiveness of PPIs.
Devil's claw has been reported to increase stomach acid, which might interfere with the effects of PPIs.
Vitamin C
Alkylating Agents
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin C have on chemotherapy.
Aluminum
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Research in animals and humans shows that vitamin C increases aluminum absorption, theoretically by chelating aluminum and keeping it in solution where it is available for absorption. In people with normal renal function, urinary excretion of aluminum will likely increase, making aluminum retention and toxicity unlikely. Patients with renal failure who take aluminum-containing compounds such as phosphate binders should avoid vitamin C supplements in doses above the recommended dietary allowances.
Antitumor Antibiotics
Theoretically, the antioxidant effects of vitamin C might reduce the effectiveness of antitumor antibiotics.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as doxorubicin. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effects, if any, antioxidants such as vitamin C have on chemotherapy.
Estrogens
Vitamin C might increase blood levels of estrogens.
Increases in plasma estrogen levels of up to 55% occur under some circumstances when vitamin C is taken concurrently with oral contraceptives or hormone replacement therapy, including topical products. It is suggested that vitamin C prevents oxidation of estrogen in the tissues, regenerates oxidized estrogen, and reduces sulfate conjugation of estrogen in the gut wall. When tissue levels of vitamin C are high, these processes are already maximized and supplemental vitamin C does not have any effect on estrogen levels. Increases in plasma estrogen levels may occur when patients who are deficient in vitamin C take supplements. Monitor these patients for estrogen-related side effects.
Fluphenazine (Prolixin)
Theoretically, vitamin C might decrease levels of fluphenazine.
In one patient there was a clinically significant decrease in fluphenazine levels when vitamin C (500 mg twice daily) was started. The mechanism is not known, and there is no further data to confirm this interaction.
Indinavir (Crixivan)
Vitamin C can modestly reduce indinavir levels.
One pharmacokinetic study shows that taking vitamin C 1 gram orally once daily along with indinavir 800 mg orally three times daily reduces the area under the concentration-time curve of indinavir by 14%. The mechanism of this interaction is unknown, but it is unlikely to be clinically significant in most patients. The effect of higher doses of vitamin C on indinavir levels is unknown.
Levothyroxine (Synthroid, Others)
Vitamin C can increase levothyroxine absorption.
Two clinical studies in adults with poorly controlled hypothyroidism show that swallowing levothyroxine with a glass of water containing vitamin C 500-1000 mg in solution reduces thyroid stimulating hormone (TSH) levels and increases thyroxine (T4) levels when compared with taking levothyroxine alone. This suggests that vitamin C increases the oral absorption of levothyroxine, possibly due to a reduction in pH.
Warfarin (Coumadin)
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Vitamin C in high doses may cause diarrhea and possibly reduce warfarin absorption. There are reports of two people who took up to 16 grams daily of vitamin C and had a reduction in prothrombin time. Lower doses of 5-10 grams daily can also reduce warfarin absorption. In many cases, this does not seem to be clinically significant. However, a case of warfarin resistance has been reported for a patient who took vitamin C 500 mg twice daily. Cessation of vitamin C supplementation resulted in a rapid increase in international normalized ratio (INR). Tell patients taking warfarin to avoid taking vitamin C in excessively high doses (greater than 10 grams daily). Lower doses may be safe, but the anticoagulation activity of warfarin should be monitored. Patients who are stabilized on warfarin while taking vitamin C should avoid adjusting vitamin C dosage to prevent the possibility of warfarin resistance.
Acetaminophen (Tylenol, Others)
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
A small pharmacokinetic study in healthy volunteers shows that taking high-dose vitamin C (3 grams) 1.5 hours after taking acetaminophen 1 gram slightly increases the apparent half-life of acetaminophen from around 2.3 hours to 3.1 hours. Ascorbic acid competitively inhibits sulfate conjugation of acetaminophen. However, to compensate, elimination of acetaminophen glucuronide and unconjugated acetaminophen increases. This effect is not likely to be clinically significant.
Aspirin
Acidification of the urine by vitamin C might increase aspirin levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction is not clinically significant.
Choline Magnesium Trisalicylate (Trilisate)
Acidification of the urine by vitamin C might increase choline magnesium trisalicylate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Niacin
Vitamin C might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as vitamin C, or to the combination. It also is not known whether it will occur in other patient populations.
Salsalate (Disalcid)
Acidification of the urine by vitamin C might increase salsalate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams/day vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Zinc
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Theoretically, zinc might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after zinc containing products.
Cephalexin (Keflex)
Zinc might decrease cephalexin levels by chelating with cephalexin in the gut and preventing its absorption.
A pharmacokinetic study shows that zinc sulfate 250 mg taken concomitantly with cephalexin 500 mg decreases peak levels of cephalexin by 31% and reduces the exposure to cephalexin by 27%. Also, taking zinc sulfate 3 hours before cephalexin decreases peak levels of cephalexin by 11% and reduces the exposure to cephalexin by 18%. By decreasing cephalexin levels, zinc might increase the risk of treatment failure. This effect does not occur when zinc is taken 3 hours after the cephalexin dose. To avoid an interaction, advise patients take zinc sulfate 3 hours after taking cephalexin.
Cisplatin (Platinol-Aq)
Theoretically, zinc might interfere with the therapeutic effects of cisplatin.
Animal research suggests that zinc stimulates tumor cell production of the protein metallothionein, which binds and inactivates cisplatin. It is not known whether zinc supplements or high dietary zinc intake can cause clinically significant interference with cisplatin therapy. Cisplatin might also increase zinc excretion.
Integrase Inhibitors
Theoretically, taking zinc along with integrase inhibitors might decrease the levels and clinical effects of these drugs.
Zinc is a divalent cation. Pharmacokinetic studies have shown that other divalent cations such as calcium and iron can decrease blood levels of the integrase inhibitor dolutegravir through chelation.
Penicillamine (Cuprimine, Depen)
Zinc might reduce the levels and clinical effects of penicillamine.
By forming an insoluble complex with penicillamine, zinc interferes with penicillamine absorption and activity. Zinc supplements reduce the efficacy of low-dose penicillamine (0.5-1 gram/day), but do not seem to affect higher doses (1-2.75 gram/day), provided dosing times are separated. Advise patients to take zinc and penicillamine at least 2 hours apart.
Quinolone Antibiotics
Zinc can decrease the levels and clinical effects of quinolones antibiotics.
Quinolones form complexes with zinc in the gastrointestinal tract, reducing absorption of both the quinolone and zinc if taken at the same time. Advise patients to take these drugs at least 2 hours before, or 4-6 hours after, zinc supplements.
Ritonavir (Norvir)
Zinc modestly reduces levels of ritonavir.
Clinical research shows that zinc might reduce serum ritonavir levels by chelating with ritonavir in the gut and preventing its absorption. In patients with HIV, ritonavir is taken with atazanavir to prevent the metabolism and increase the effects of atazanavir. A pharmacokinetic study shows that, in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate (Solvazinc tablets) 125 mg as a single dose or as multiple daily doses for 2 weeks reduces plasma levels of ritonavir by about 16%. However, atazanavir levels still remains high enough to prevent HIV virus replication. Therefore, the decrease in ritonavir levels is not likely to be clinically significant.
Tetracycline Antibiotics
Zinc might reduce levels of tetracycline antibiotics.
Tetracyclines form complexes with zinc in the gastrointestinal tract, which can reduce absorption of both the tetracycline and zinc when taken at the same time. Taking zinc sulfate 200 mg with tetracycline reduces absorption of the antibiotic by 30% to 40%. Demeclocycline and minocycline cause a similar interaction. However, doxycycline does not seem to interact significantly with zinc. Advise patients to take tetracyclines at least 2 hours before, or 4-6 hours after, zinc supplements to avoid any interactions.
Amiloride (Midamor)
Amiloride can modestly reduce zinc excretion and increase zinc levels.
Clinical research shows that amiloride can reduce urinary zinc excretion, especially at doses of 10 mg per day or more. This zinc-sparing effect can help to counteract zinc losses caused by thiazide diuretics, but it is unlikely to cause zinc toxicity at usual amiloride doses. The other potassium-sparing diuretics, spironolactone (Aldactone) and triamterene (Dyrenium), do not seem to have a zinc-sparing effect.
Atazanavir (Reyataz)
Zinc modestly reduces levels of atazanavir, although this effect does not seem to be clinically significant.
Clinical research shows that zinc might decrease serum atazanavir levels by chelating with atazanavir in the gut and preventing its absorption. Although a single dose of zinc sulfate (Solvazinc tablets) 125 mg orally does not affect atazanavir concentrations in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate 125 mg daily for 2 weeks reduces plasma levels of atazanavir by about 22% in these patients. However, despite this decrease, atazanavir levels still remain at high enough concentrations for the prevention of HIV virus replication.
Copper
Penicillamine (Cuprimine, Depen)
Theoretically, taking copper with penicillamine might decrease the absorption of penicillamine; separate dosing by at least 2 hours.
Copper chelates penicillamine, which decreases its absorption and may reduce its clinical effects.
Contraceptive Drugs
Theoretically, taking copper with contraceptive drugs might increase the levels and toxic effects of copper.
A meta-analysis of clinical studies suggests that chronic use of oral contraceptives increases serum copper levels by a mean of 57 mcg/dL. In most people, this resulted in levels above the normal reference range for copper.
Brand information
Manufacturer and brand details for Inflameric, from the product label.
OL Olympian Labs
See all OL Olympian Labs products- Name
- Olympian Labs, Inc.
- City
- Phoenix
- State
- AZ
- ZipCode
- 85027
- Phone Number
- 1.800.473.5883
- Web Address
- www.olympianlabs.com
Inflameric by OL Olympian Labs: Common Questions
Does Inflameric by OL Olympian Labs interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take Inflameric if I'm pregnant or breastfeeding?
Does Inflameric contain any digestive enzymes?
What's the green tea extract in Inflameric for?
Will Inflameric cause stomach upset?
Can I take Inflameric with my blood pressure or diabetes medications?
What does the proprietary herbal blend contain?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Inflameric is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Inflameric’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin C
Interacts with 207 drugsVitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for immune function, collagen, and acts as an...
Read the full Vitamin C monograph → Herb & supplement monographZinc
Interacts with 67 drugsZinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but supplements can help correct or prevent a defici...
Read the full Zinc monograph → Herb & supplement monographCat's Claw
Interacts with 962 drugsCat's claw is a South American vine traditionally used for inflammation, joint pain, and immune support. Some small studies hint it may help with arthritis symptoms, but the overall evidence...
Read the full Cat's Claw monograph → Herb & supplement monographGymnema
Interacts with 851 drugsGymnema is an Ayurvedic herb best known for possibly helping lower blood sugar and reducing the taste of sweetness on the tongue. Some early human studies are encouraging for blood sugar sup...
Read the full Gymnema monograph → Herb & supplement monographDevil's Claw
Interacts with 804 drugsDevil's claw is a southern African plant used mainly for arthritis and back pain, and some studies suggest it may help ease these types of discomfort. The evidence is moderate at best, and p...
Read the full Devil's Claw monograph → Herb & supplement monographYucca
Yucca is a desert plant traditionally used for joint pain, arthritis, and digestion, and it contains compounds called saponins thought to have anti-inflammatory effects. Human evidence for t...
Read the full Yucca monograph → Herb & supplement monographCopper
Interacts with 31 drugsCopper is an essential trace mineral your body needs in small amounts for making red blood cells, supporting nerves and bones, and helping enzymes work. Most people get enough copper from fo...
Read the full Copper monograph → Herb & supplement monographProteolytic Enzymes (proteases)
Proteolytic enzymes are proteins that help break down other proteins, and common examples include bromelain (from pineapple), papain (from papaya), trypsin, chymotrypsin, and pancreatin. Peo...
Read the full Proteolytic Enzymes (proteases) monograph → Herb & supplement monographLipase
Lipase is a digestive enzyme that helps your body break down dietary fats. It is well established as part of prescription pancreatic enzyme therapy for people who cannot make enough of their...
Read the full Lipase monograph → Herb & supplement monographGreen Tea
Interacts with 1,293 drugsGreen tea is a popular beverage rich in antioxidants called catechins, and drinking it in normal amounts is considered safe for most people. Concentrated green tea extracts are a different s...
Read the full Green Tea monograph → Herb & supplement monographTurmeric
Interacts with 1,133 drugsTurmeric is a popular spice whose main active compounds, curcuminoids, are studied mostly for inflammation and joint pain. Some research is promising, but quality is mixed and curcumin is po...
Read the full Turmeric monograph → Herb & supplement monographBoswellia Serrata
Interacts with 952 drugsBoswellia serrata is a tree resin used in traditional medicine, mainly for joint pain and inflammation. Some studies suggest it may help with osteoarthritis symptoms, but the overall evidenc...
Read the full Boswellia Serrata monograph →Sources & How We Checked
Inflameric's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 540 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Vitamin C 51 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Back DJ, Breckenridge AM, MacIver M, et al. Interaction of ethinyloestradiol with ascorbic acid in man. Br Med J (Clin Res Ed) 1981;282:1516.
- Morris JC, Beeley L, Ballantine N. Interaction of ethinyloestradiol with ascorbic acid in man [letter]. Br Med J (Clin Res Ed) 1981;283:503.
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Dwyer JH, Merz NB, Shirocre AM, et al. Progression of early atherosclerosis and intake of vitamin C and vitamin E from supplements and food. The Los Angeles Atherosclerosis Study. 41st Annual Conference on Cardiovascular Disease Epidemiology and Prevent
- Levine M, Rumsey SC, Daruwala R, et al. Criteria and recommendations for vitamin C intake. JAMA 1999;281:1415-23. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Houston JB, Levy G. Drug biotransformation interactions in man VI: Acetaminophen and ascorbic acid. J Pharm Sci 1976;65:1218-21. PubMed
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Rosenthal G. Interaction of ascorbic acid and warfarin. JAMA 1971;215:1671. DOI
- Hume R, Johnstone JM, Weyers E. Interaction of ascorbic acid and warfarin. JAMA 1972;219:1479. DOI
- Smith EC, Skalski RJ, Johnson GC, Rossi GV. Interaction of ascorbic acid and warfarin. JAMA 1972;221:1166. DOI
- Traxer O, Huet B, Poindexter J, et al. Effect of ascorbic acid consumption on urinary stone risk factors. J Urol 2003;170:397-401.. PubMed
- Domingo JL, Gomez M, Llobet JM, Richart C. Effect of ascorbic acid on gastrointestinal aluminum absorption (letter). Lancet 1991;338:1467.
- Domingo JL, Gomez M, Llobet JM, Corbella J. Influence of some dietary constituents on aluminum absorption and retention in rats. Kidney Int 1991;39:598-601. PubMed
- Partridge NA, Regnier FE, White JL, Hem SL. Influence of dietary constituents on intestinal absorption of aluminum. Kidney Int 1989;35:1413-7. PubMed
- Mc Leod DC, Nahata MC. Inefficacy of ascorbic acid as a urinary acidifier (letter). N Engl J Med 1977;296:1413. DOI
- Hansten PD, Hayton WL. Effect of antacid and ascorbic acid on serum salicylate concentration. J Clin Pharmacol 1980;20:326-31. PubMed
- Dysken MW, Cumming RJ, Channon RA, Davis JM. Drug interaction between ascorbic acid and fluphenazine. JAMA 1979;241:2008. DOI
- Vihtamaki T, Parantainen J, Koivisto AM, et al. Oral ascorbic acid increases plasma oestradiol during postmenopausal hormone replacement therapy. Maturitas 2002;42:129-35. PubMed
- Slain D, Amsden JR, Khakoo RA, et al. Effect of high-dose vitamin C on the steady-state pharmacokinetics of the protease inhibitor indinavir in healthy volunteers. Pharmacotherapy 2005;25:165-70. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Feetam CL, Leach RH, Meynell MJ. Lack of a clinically important interaction between warfarin and ascorbic acid. Toxicol Appl Pharmacol 1975;31:544-7. PubMed
- Weintraub M, Griner PF. Warfarin and ascorbic acid: lack of evidence for a drug interaction. Toxicol Appl Pharmacol 1974;28:53-6. PubMed
- Lee DH, Folsom AR, Harnack L, et al. Does supplemental vitamin C increase cardiovascular disease risk in women with diabetes? Am J Clin Nutr 2004;80:1194-200. PubMed
- Taylor EN, Stampfer MJ, Curhan GC. Dietary factors and the risk of incident kidney stones in men: new insights after 14 years of follow-up. J Am Soc Nephrol 2004;15:3225-32. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Fairweather-Tait S, Hickson K, McGaw B, et al. Orange juice enhances aluminium absorption from antacid preparation. Eur J Clin Nutr. 1994;48(1):71-3.
- Gruenwald, J., Graubaum, H. J., Busch, R., and Bentley, C. Safety and tolerance of ester-C compared with regular ascorbic acid. Adv.Ther. 2006;23(1):171-178.
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Einerson, B., Nathorn, C., Kitiyakara, C., Sirada, M., and Thamlikitkul, V. The efficacy of ascorbic acid in suboptimal responsive anemic hemodialysis patients receiving erythropoietin: a meta-analysis. J Med.Assoc.Thai. 2011;94 Suppl 1:S134-S146.
- Li, G., Li, L., Yu, C., and Chen, L. Effect of vitamins C and E supplementation on Helicobacter pylori eradication: a meta-analysis. Br.J Nutr 2011;106(11):1632-1637.
- Chen X, Shen L, Gu X, et al. High-dose supplementation with vitamin C--induced pediatric urolithiasis: the first case report in a child and literature review. Urology. 2014;84(4):922-4. PubMed
- Sattar A, Willman JE, Kolluri R. Possible warfarin resistance due to interaction with ascorbic acid: case report and literature review. Am J Health Syst Pharm. 2013;70(9):782-6. PubMed
- Yaich S, Chaabouni Y, Charfeddine K, et al. Secondary oxalosis due to excess vitamin C intake: a cause of graft loss in a renal transplant recipient. Saudi J Kidney Dis Transpl. 2014;25(1):113-6. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Rumbold A, Ota E, Nagata C, Shahrook S, Crowther CA. Vitamin C supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004072. PubMed
- Seo MS, Kim JK, Shim JY. High-dose vitamin C promotes regression of multiple pulmonary metastases originating from hepatocellular carcinoma. Yonsei Med J. 2015;56(5):1449-52. PubMed
- Skelin M, Lucijanic T, Amidzic Klaric D, et al. Factors Affecting Gastrointestinal Absorption of Levothyroxine: A Review. Clin Ther. 2017 Feb;39(2):378-403. PubMed
- Jiang K, Tang K, Liu H, Xu H, Ye Z, Chen Z. Ascorbic acid supplements and kidney stones incidence among men and women: a systematic review and meta-analysis. Urol J. 2019;16(2):115-120.
- Thomas S, Patel D, Bittel B, et al. Effect of High-Dose Zinc and Ascorbic Acid Supplementation vs Usual Care on Symptom Length and Reduction Among Ambulatory Patients With SARS-CoV-2 Infection: The COVID A to Z Randomized Clinical Trial. JAMA Netw Open. 2 PubMed
- Giffen MA, McLemore JL. Hyperoxalosis Secondary to Intravenous Vitamin C Administration as a Non-Allopathic Treatment for Cancer. Acad Forensic Pathol 2019;9(1-2):118-126. PubMed
- Maike A, Sturgill D, Gallan A. Oxalate Nephropathy in a Renal Transplant Recipient After Receiving High Dose Ascorbic Acid. Am J Med Sci 2021. PubMed
- Shen ZY, Chen YR, Wang MC, Chang SS. High-dose vitamin C-induced acute oxalate nephropathy in a renal transplant recipient: a case report and literature review. Asian J Surg 2022. PubMed
- Yanase F, Spano S, Maeda A, et al. Mega-dose sodium ascorbate: a pilot, single-dose, physiological effect, double-blind, randomized, controlled trial. Crit Care 2023;27(1):371. PubMed
- Sharma Y, Sumanadasa S, Shahi R, et al. Efficacy and safety of vitamin C supplementation in the treatment of community-acquired pneumonia: a systematic review and meta-analysis with trial sequential analysis. Sci Rep 2024;14(1):11846. PubMed
- Pejcic AV, Petrovic NZ, Djordjic MD, Milosavljevic MN. Vitamin C Levels in Pregnant Women and the Efficacy of Vitamin C Supplements in Preventing Premature Rupture of Membranes: A Systematic Review and Meta-Analysis. Balkan Med J 2024;41(4):248-260. PubMed
Zinc 88 references
- Barceloux DG. Zinc. J Toxicol Clin Toxicol 1999;37:279-92.
- Eby GA, Davis DR, Halcomb WW. Reduction in duration of common colds by zinc gluconate lozenges in a double-blind study. Antimicrob Agents Chemother 1984;25:20-4. DOI
- Smith DS, Helzner EC, Nuttall CE Jr, et al. Failure of zinc gluconate in treatment of acute upper respiratory tract infections. Antimicrob Agents Chemother 1989;33:646-8. PubMed
- Blondeau JM. Expanded activity and utility of the new fluoroquinolones: a review. Clin Ther 1999;21:3-40. PubMed
- Reyes AJ, Olhaberry JV, Leary WP, et al. Urinary zinc excretion, diuretics, zinc deficiency and some side-effects of diuretics. S Afr Med J 1983;64:936-41.
- Kugelmas M. Preliminary observation: oral zinc sulfate replacement is effective in treating muscle cramps in cirrhotic patients. J Am Coll Nutr 2000;19:13-5. PubMed
- Hebel SK, ed. Drug Facts and Comparisons. 52nd ed. St. Louis: Facts and Comparisons, 1998.
- Chan S, Gerson B, Subramaniam S. The role of copper, molybdenum, selenium, and zinc in nutrition and health. Clin Lab Med 1998;18:673-85. DOI
- Brewer GJ, Yuzbasiyan-Gurkan V, Johnson V, et al. Treatment of Wilson's disease with zinc: XI. Interaction with other anticopper agents. J Am Coll Nutr 1993;12:26-30. PubMed
- Fosmire GJ. Zinc toxicity. Am J Clin Nutr 1990;51:225-7.
- Lomaestro BM, Bailie GR. Absorption interactions with fluoroquinolones. 1995 update. Drug Saf 1995;12:314-33. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Seelig MS. Auto-immune complications of D-penicillamine - A possible result of zinc and magnesium depletion and of pyridoxine inactivation. J Am Coll Nutr 1982;1:207-14. PubMed
- Neuvonen PJ. Interactions with the absorption of tetracyclines. Drugs 1976;11:45-54.. PubMed
- Hirt M, Nobel S, Barron E. Zinc nasal gel for the treatment of common cold symptoms: A double-blind, placebo-controlled trial. Ear Nose Throat J 2000;79:778-82.. DOI
- Simkin PA. Oral zinc sulphate in rheumatoid arthritis. Lancet 1976;2:539-42. PubMed
- Wray D. A double-blind trial of systemic zinc sulfate in recurrent aphthous stomatitis. Oral Surg Oral Med Oral Pathol 1982;53:469-72. PubMed
- Douglas RM, Miles HB, Moore BW, et al. Failure of effervescent zinc acetate lozenges to alter the course of upper respiratory tract infections in Australian adults. Antimicrob Agents Chemother 1987;31:1263-5. PubMed
- Lagiou P, Wuu J, Trichopoulou A, et al. Diet and benign prostatic hyperplasia: a study in Greece. Urology 1999;54:284-90. PubMed
- Ewing CI, Gibbs AC, Ashcroft C, David TJ. Failure of oral zinc supplementation in atopic eczema. Eur J Clin Nutr 1991;45:507-10.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Age-Related Eye Disease Study Research Group. A randomized, placebo-controlled, clinical trial of high-dose supplementation with vitamins C and E, beta carotene, and zinc for age-related macular degeneration and vision loss. AREDS report no. 8. Arch Oph
- Greenberg JE, Lynn M, Kirsner RS, et al. Mucocutaneous pigmented macule as a result of zinc deposition. J Cutan Pathol 2002;29:613-5. PubMed
- Godfrey HR, Godfrey NJ, Godfrey JC, Riley D. A randomized clinical trial on the treatment of oral herpes with topical zinc oxide/glycine. Altern Ther Health Med 2001;7:49-56.
- Turner RB. Ineffectiveness of intranasal zinc gluconate for prevention of experimental rhinovirus colds. Clin Infect Dis 2001;33:1865-70. PubMed
- Belongia EA, Berg R, Liu K. A randomized trial of zinc nasal spray for the treatment of upper respiratory illness in adults. Am J Med 2001;111:103-8. PubMed
- Mossad SB. Effect of zincum gluconicum nasal gel on the duration and symptom severity of the common cold in otherwise healthy adults. QJM 2003;96:35-43. DOI
- Leitzmann MF, Stampfer MJ, Wu K, et al. Zinc supplement use and risk of prostate cancer. J Natl Cancer Inst 2003;95:1004-7.. PubMed
- Jafek BW, Linschoten M, Murrow BW. Zicam Induced Anosmia. American Rhinologic Society 49th Annual Fall Scientific Meeting abstract. Orlando, Florida. September 20, 2003. http://app.american-rhinologic.org/programs/2003ARSFallProgram071503.pdf (Accessed 24
- Uebayashi H, Hatanaka T, Kanemura F, Tonosaki K. Acute anosmia in the mouse: behavioral discrimination among the four basic taste substances. Physiol Behav 2001;72:291-6.. PubMed
- Barrett S. Zicam Marketers Sued. United States District Court Western District of Michigan Southern Division, Filed October 14, 2003, Case No. 4:03CV0146.
- Bilici M, Yildirim F, Kandil S, et al. Double-blind, placebo-controlled study of zinc sulfate in the treatment of attention deficit hyperactivity disorder. Prog Neuropsychopharmacol Biol Psychiatry 2004;28:181-90.. PubMed
- Polk RE, Healy DP, Sahai J, et al. Effect of ferrous sulfate and multivitamins with zinc on absorption of ciprofloxacin in normal volunteers. Antimicrob Agents Chemother 1989;33:1841-4. PubMed
- Mery C, Delrieu F, Ghozlan R, et al. Controlled trial of D-penicillamine in rheumatoid arthritis. Dose effect and the role of zinc. Scand J Rheumatol 1976;5:241-7. PubMed
- Penttila O, Hurme H, Neuvonen PJ. Effect of zinc sulfate on the absorption of tetracycline and doxycycline in man. Eur J Clin Pharmacol 1975;9:131-4.
- Kondo Y, Yamagata K, Satoh M, et al. Optimal administration schedule of cisplatin for bladder tumor with minimal induction of metallothionein. J Urol 2003;170:2467-70. PubMed
- Doz F, Berens ME, Deschepper CF, et al. Experimental basis for increasing the therapeutic index of cis-diamminedicarboxylatocyclobutaneplatinum(II) in brain tumor therapy by a high-zinc diet. Cancer Chemother Pharmacol 1992;29:219-26.
- Wester PO. Urinary zinc excretion during treatment with different diuretics. Acta Med Scand 1980;208:209-12. PubMed
- Golik A, Modai D, Weissgarten J, et al. Hydrochlorothiazide-amiloride causes excessive urinary zinc excretion. Clin Pharmacol Ther 1987;42:42-4. PubMed
- Leary WP, Reyes AJ, Van der Byl K. Urinary magnesium and zinc excretion after two different single doses of amiloride in healthy adults. Curr Ther Res 1983;34:205-16.
- McBride K, Slotnick B, Margolis FL. Does intranasal application of zinc sulfate produce anosmia in the mouse? An olfactometric and anatomical study. Chem Senses 2003;28:659-70. PubMed
- Burd GD. Morphological study of the effects of intranasal zinc sulfate irrigation on the mouse olfactory epithelium and olfactory bulb. Microsc Res Tech 1993;24:195-213. PubMed
- Ducray A, Bondier JR, Michel G, et al. Recovery following peripheral destruction of olfactory neurons in young and adult mice. Eur J Neurosci 2002;15:1907-17. PubMed
- Mayer AD, Rosenblatt JS. Peripheral olfactory deafferentation of the primary olfactory system in rats using ZnSO4 nasal spray with special reference to maternal behavior. Physiol Behav 1993;53:587-92. PubMed
- DeCook CA, Hirsch AR. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Tisdall FF, Brown A, Defries RD. Persistent anosmia following zinc sulfate nasal spraying. JPed 1938;18:60-2. DOI
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Public Health Advisory. Loss of sense of smell with intranasal cold remedies containing zinc. U.S. Food and Drug Administration, June 16, 2009. Available at: http://www.fda.gov/Drugs/DrugSafety/PublicHealthAdvisories/ucm166059.htm (Accessed 16 June 2009)
- Dooren JC. FDA warns against use of Zicam. The Wall Street Journal, June 16, 2009. Available at: http://online.wsj.com/article/SB124516778692319231.html#mod=djemHL?mg=com-wsj (Accessed 16 June 2009).
- Alexander TH, Davidson TM. Intranasal zinc and anosmia: the zinc-induced anosmia syndrome. Laryngoscope 2006;116:217-20.
- Health Canada / GlaxoSmithKline Consumer Healthcare. Association of long-term, excessive use of zinc-containing Poli-Grip products with myeloneuropathy and blood dyscrasias. February 18, 2010. Available at: http://hc-sc.gc.ca/dhp-mps/alt_formats/pdf/medef
- GlaxoSmithKline Consumer Advisory. GlaxoSmithKline (GSK) warns about a potential health risk associated with long-term, excessive use of GSK's zinc-containing denture adhesives Super Polygrip Original, Ultra Fresh and Extra Care. February 18, 2010. Availa
- Science M, Johnstone J, Roth DE, et al. Zinc for the treatment of the common cold: a systematic review and meta-analysis of randomized controlled trials. CMAJ 2012;184:E551-61. PubMed
- Castilla-Higuero, L., Romero-Gomez, M., Suarez, E., and Castro, M. Acute hepatitis after starting zinc therapy in a patient with presymptomatic Wilson's disease. Hepatology 2000;32(4 Pt 1):877. PubMed
- Sharquie, K. E., Najim, R. A., Farjou, I. B., and Al Timimi, D. J. Oral zinc sulphate in the treatment of acute cutaneous leishmaniasis. Clin.Exp.Dermatol. 2001;26(1):21-26. PubMed
- Dreno, B., Moyse, D., Alirezai, M., Amblard, P., Auffret, N., Beylot, C., Bodokh, I., Chivot, M., Daniel, F., Humbert, P., Meynadier, J., and Poli, F. Multicenter randomized comparative double-blind controlled clinical trial of the safety and efficacy of
- Moore, R. Bleeding gastric erosion after oral zinc sulphate. Br.Med J 3-25-1978;1(6115):754. PubMed
- Jafek, B. W., Linschoten, M. R., and Murrow, B. W. Anosmia after intranasal zinc gluconate use. Am J Rhinol. 2004;18(3):137-141. DOI
- Simonart, T. and de, Maertelaer, V. Systemic treatments for cutaneous warts: a systematic review. J Dermatolog.Treat. 2012;23(1):72-77. PubMed
- Cochran, R. J., Tucker, S. B., and Flannigan, S. A. Topical zinc therapy for acne vulgaris. Int.J Dermatol. 1985;24(3):188-190. DOI
- Morgan, A. A. Bleeding gastric erosion after oral zinc sulphate. Br.Med.J. 5-13-1978;1(6122):1283-1284. PubMed
- Murphy, J. V. Intoxication following ingestion of elemental zinc. JAMA 6-22-1970;212(12):2119-2120.
- Lang, C. J., Rabas-Kolominsky, P., Engelhardt, A., Kobras, G., and Konig, H. J. Fatal deterioration of Wilson's disease after institution of oral zinc therapy. Arch Neurol. 1993;50(10):1007-1008. PubMed
- Fjellner, B. Drug-induced lupus erythematosus aggravated by oral zinc therapy. Acta Derm.Venereol. 1979;59(4):368-370. DOI
- Varas Lorenzo, M. J. Zinc acexamate and ranitidine in the short- and mid-term management of gastroduodenal ulcers. Curr Ther Res 21986;39:19-29.
- Bosch, F. and Jimenez, E. Post-marketing surveillance of zinc acexamate in peptic ulcer treatment. Clin Trials J 1990;27:301-312.
- DeCook, C. A. and Hirsch, A. R. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Crown LA, May JA. Zinc toxicity: denture adhesives, bone marrow failure and polyneuropathy. Tenn Med. 2012 Feb;105(2):39-40, 42.
- Dadamio J, Van Tournout M, Teughels W, Dekeyser C, Coucke W, Quirynen M. Efficacy of different mouthrinse formulations in reducing oral malodour: a randomized clinical trial. J Clin Periodontol. 2013 May;40(5):505-13. PubMed
- Moyle G, Else L, Jackson A, Back D, Yapa MH, Seymour N, Ringner-Nackter L, Karolia Z, Gazzard B, Boffito M. Coadministration of atazanavir-ritonavir and zinc sulfate: impact on hyperbilirubinemia and pharmacokinetics. Antimicrob Agents Chemother. 2013 Aug PubMed
- Zittel S, Ufer F, Gerloff C, Münchau A, Rosenkranz M. Severe myelopathy after denture cream use--is copper deficiency or excess zinc the cause? Clin Neurol Neurosurg. 2014 Jun;121:17-8. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Guidelines for the Use of Antiretroviral Agents in HIV-1-Infected Adults and Adolescents: Drug Interactions between Integrase Inhibitors and Other Drugs. AIDSinfo. July 14, 2016. Available at: https://aidsinfo.nih.gov/guidelines/html/1/adult-and-adolescen
- Ding Y, Jia YY, Li F, et al. The effect of staggered administration of zinc sulfate on the pharmacokinetics of oral cephalexin. Br J Clin Pharmacol. 2012 Mar;73(3):422-7. PubMed
- Fallah R, Sabbaghzadegan S, Karbasi SA, Binesh F. Efficacy of zinc sulfate supplement on febrile seizure recurrence prevention in children with normal serum zinc level: A randomised clinical trial. Nutrition. 2015;31(11-12):1358-61. PubMed
- Lazzerini M, Wanzira H. Oral zinc for treating diarrhoea in children. Cochrane Database Syst Rev. 2016;12:CD005436. PubMed
- Mahmoud AM, Al-Alem U, Dabbous F, et al. Zinc intake and risk of prostate cancer: Case-control study and meta-analysis. PLoS One. 2016;11(11):e0165956. PubMed
- Nagraj SK, George RP, Shetty N, Levenson D, Ferraiolo DM, Shrestha A. Interventions for managing taste disturbances. Cochrane Database Syst Rev. 2017 Dec 20;12(12):CD010470. PubMed
- Yee BE, Richards P, Sui JY, Marsch AF. Serum zinc levels and efficacy of zinc treatment in acne vulgaris: A systematic review and meta-analysis. Dermatol Ther. 2020:e14252. PubMed
- Janyajirawong R, Vilaichone RK, Sethasine S. Efficacy of zinc supplement in minimal hepatic encephalopathy: A prospective, randomized controlled study (Zinc-MHE Trial). Asian Pac J Cancer Prev 2021;22(9):2879-2887. PubMed
- Nakano M, Nakamura Y, Miyazaki A, Takahashi J. Zinc pharmacotherapy for elderly osteoporotic patients with zinc deficiency in a clinical setting. Nutrients 2021;13(6):1814. PubMed
- Tolino E, Skroza N, Mambrin A, et al. An open-label study comparing oral zinc to lymecycline in the treatment of acne vulgaris. J Clin Aesthet Dermatol 2021;14(5):56-58.
- Hunter J, Arentz S, Goldenberg J, et al. Zinc for the prevention or treatment of acute viral respiratory tract infections in adults: a rapid systematic review and meta-analysis of randomised controlled trials. BMJ Open. 2021;11(11):e047474. PubMed
- Yamazaki K, Kageyama H, Fujiyama T, Ito T, Urano S, Honda T. A case of systemic contact dermatitis due to zinc supplements. Int J Dermatol 2022. PubMed
- Magham K, Han J, Eilbert W, Bunney EB. Severe copper deficiency anemia caused by zinc supplement use. Am J Emerg Med 2023;72:222. PubMed
- Sivakumar RR, Chinnaiah Govindareddy D, Sahoo J, Bobby Z, Chinnakali P. Effect of daily zinc supplementation for 12 weeks on serum thyroid auto-antibody levels in children and adolescents with autoimmune thyroiditis - a randomized controlled trial. J Pedi PubMed
- AlDhasee O, AlMalki H, AlKharashi N, AlJeraisy N, Al Deeb M. Acute zinc sulfate overdose: clinical presentation and management. BMJ Case Rep 2025;18(1):e263899. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Proteolytic Enzymes (proteases) 3 references
- Weeks JA, Harper RA, Simon RA, Burdick JD. Assessment of sensitization risk of a laundry pre-spotter containing protease. Cutan Ocul Toxicol. 2011;30(4):272-9. PubMed
- Marquès LI, Lara S, Abós T, Bartolomé B. Occupational rhinitis due to pepsin. J Investig Allergol Clin Immunol. 2006;16(2):136-7. DOI
- Cartier A, Malo JL, Pineau L, Dolovich J. Occupational asthma due to pepsin. J Allergy Clin Immunol. 1984;73(5 Pt 1):574-7. PubMed
See these in context on the Proteolytic Enzymes (proteases) monograph →
Lipase 1 reference
- Casper C, Hascoet JM, Ertl T, et al. Recombinant bile salt-stimulated lipase in preterm infant feeding: A randomized phase 3 study. PLoS One. 2016;11(5):e0156071. PubMed
Copper 11 references
- Murry JJ, Healy MD. Drug-mineral interactions: a new responsibility for the hospital dietician. J Am Diet Assoc 1991;91:66-73.
- Campbell IA, Elmes PC. Ethambutol and the eye: zinc and copper (letter). Lancet 1975;2:711. DOI
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Kozak SF, Inderlied CB, Hsu HY, et al. The role of copper on ethambutol's antimicrobial action and implications for ethambutol-induced optic neuropathy. Diag Microbiol Infect Dis 1998;30:83-7. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Cantilena LR, Klaassen CD. The effect of chelating agents on the excretion of endogenous metals. Toxicol Appl Pharmacol 1982;63:344-50.
- Babic Z, Tariba B, Kovacic J, Pizent A, Varnai VM, Macan J. Relevance of serum copper elevation induced by oral contraceptives: a meta-analysis. Contraception. 2013 Jun;87(6):790-800. PubMed
- Qui Q, Zhang F, Zhu W, Wu J, Liang M. Copper in diabetes mellitus: a meta-analysis and systematic review of plasma and serum studies. Biol Trace Elem Res 2017;177(1):53-63.
- Walker-Smith PK, Keith DJ, Kennedy CT, Sansom JE. Allergic contact dermatitis caused by copper. Contact Dermatitis 2016;75(3):186-7. PubMed
- Gallentine A. Third-degree burn on the neuropathic lower extremity in a patient with diabetes while wearing a copper-containing compression sock: a case report. Wound Manag Prev 2021;67(12):26-29. DOI
- Chung KJ, Chin YM, Wong MS, Sanmugam A, Singaravel S, Nah SA. Effectiveness of table salt versus copper sulphate in treating umbilical granuloma: A pilot randomized controlled trial. J Pediatr Surg 2022;57(2):261-265. PubMed
Cat's Claw 16 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Budzinski JW, Foster BC, Vandenhoek S, Arnason JT. An in vitro evaluation of human cytochrome P450 3A4 inhibition by selected commercial herbal extracts and tinctures. Phytomedicine 2000;7:273-82. PubMed
- Sandoval M, Charbonnet RM, Okuhama NN, et al. Cat's claw inhibits TNFalpha production and scavenges free radicals: role in cytoprotection. Free Radic Biol Med 2000;29:71-78.
- Müller AC, Kanfer I. Potential pharmacokinetic interactions between antiretrovirals and medicinal plants used as complementary and African traditional medicines. Biopharm Drug Dispos. 2011;32(8):458-70. PubMed
- Sheng, Y., Bryngelsson, C., and Pero, R. W. Enhanced DNA repair, immune function and reduced toxicity of C-MED-100, a novel aqueous extract from Uncaria tomentosa. J Ethnopharmacol. 2000;69(2):115-126. PubMed
- Lamm, S., Sheng, Y., and Pero, R. W. Persistent response to pneumococcal vaccine in individuals supplemented with a novel water soluble extract of Uncaria tomentosa, C-Med-100. Phytomedicine 2001;8(4):267-274.
- Sheng, Y., Li, L., Holmgren, K., and Pero, R. W. DNA repair enhancement of aqueous extracts of Uncaria tomentosa in a human volunteer study. Phytomedicine 2001;8(4):275-282.
- Chen, C. X., Jin, R. M., Li, Y. K., Zhong, J., Yue, L., Chen, S. C., and Zhou, J. Y. Inhibitory effect of rhynchophylline on platelet aggregation and thrombosis. Zhongguo Yao Li Xue.Bao. 1992;13(2):126-130.
- Flythe, J. E., Rueda, J. F., Riscoe, M. K., and Watnick, S. Silicate nephrolithiasis after ingestion of supplements containing silica dioxide. Am.J.Kidney Dis. 2009;54(1):127-130. PubMed
- Zhou, J. and Zhou, S. Antihypertensive and neuroprotective activities of rhynchophylline: the role of rhynchophylline in neurotransmission and ion channel activity. J.Ethnopharmacol. 10-28-2010;132(1):15-27. PubMed
- Zhou, J. Y. and Zhou, S. W. Isorhynchophylline: A plant alkaloid with therapeutic potential for cardiovascular and central nervous system diseases. Fitoterapia 2012;83(4):617-626. PubMed
- Hemingway, S. R. and Phillipson, J. D. Proceedings: Alkaloids from S. American species of Uncaria (Rubiaceae). J.Pharm.Pharmacol. 1974;26 Suppl:113P.
- Hilepo, J. N., Bellucci, A. G., and Mossey, R. T. Acute renal failure caused by 'cat's claw' herbal remedy in a patient with systemic lupus erythematosus. Nephron 1997;77(3):361. PubMed
- De Paula LCL, Fonseca F, Perazzo F, et al. Uncaria tomentosa (cat's claw) improves quality of life in patients with advanced solid tumors. J Altern Complement Med. 2015;21(1):22-30.
- Portalatin G, Shettigar S, Carrion-Rodriguez A, et al. Ketogenic-Diet Shake Containing Uncaria tomentosa-Associated Acute Interstitial Nephritis. Case Rep Nephrol Dial 2022;12(3):219-225.
- Lei S, Guo A, Lu J, et al. Activation of PXR causes drug interactions with Paxlovid in transgenic mice. Acta Pharm Sin B 2023;13(11):4502-4510. PubMed
Gymnema 12 references
- Shanmugasundaram ER, Rajeswari G, Baskaran K, et al. Use of Gymnema sylvestre leaf extract in the control of blood glucose in insulin-dependent diabetes mellitus. J Ethnopharmacol 1990;30:281-94. PubMed
- Baskaran K, Kizar Ahamath B, Radha Shanmugasundaram K, Shanmugasundaram ER. Antidiabetic effect of leaf extract from Gymnema sylvestre in non-insulin-dependent diabetes mellitus patients. J Ethnopharmacol 1990;30:295-300.
- Kamble B, Gupta A, Moothedath I, Khatal L, Janrao S, Jadhav A, et al. Effects of Gymnema sylvestre extract on the pharmacokinetics and pharmacodynamics of glimepiride in streptozotocin induced diabetic rats. Chem Biol Interact. 2016;245:30-8. PubMed
- Tiwari P, Mishra BN, Sangwan NS. Phytochemical and pharmacological properties of Gymnema sylvestre: an important medicinal plant. Biomed Res Int. 2014; 2014:830285.
- Fabio GD, Romanucci V, De Marco A, Zarrelli A. Triterpenoids from Gymnema sylvestre and their pharmacological activities. Molecules. 2014;19(8):10956-81. PubMed
- Shiyovich A, Sztarkier I, Nesher L. Toxic hepatitis induced by Gymnema sylvestre, a natural remedy for type 2 diabetes mellitus. Am J Med Sci. 2010;340(6):514-7. PubMed
- Zuniga LY, Gonzalez-Ortiz M, Martinez-Abundis E. Effect of gymnema sylvestre administration on metabolic syndrome, insulin sensitivity, and insulin secretion. J Med Food. 2017 Aug;20(8):750-54.
- Rammohan B, Samit K, Chinmoy D, et al. Human cytochrome P450 enzyme modulation by gymnema sylvestre: a predictive safety evaluation by LC-MS/MS. Pharmacogn Mag. 2016 Jul;12(Suppl 4):S389-S394.
- Vaghela M, Sahu N, Kharkar P, Pandita N. In vivo pharmacokinetic interaction by ethanolic extract of gymnema sylvestre with CYP2C9 (tolbutamide), CYP3A4 (amlodipine) and CYP1A2 (phenacetin) in rats. Chem Biol Interact. 2017 Dec 25;278:141-151. PubMed
- Vaghela M, Iyer K, Pandita N. In vitro inhibitory effect of gymnema sylvestre extracts and total gymnemic acids fraction on select cytochrome P450 activities in rat liver microsomes. Eur J Drug Metab Pharmacokinet. 2017 Oct 10. PubMed
- Gaytán Martínez LA, Sánchez-Ruiz LA, Zuñiga LY, González-Ortiz M, Martínez-Abundis E. Effect of Gymnema sylvestre administration on glycemic control, insulin secretion, and insulin sensitivity in patients with impaired glucose tolerance. J Med Food. 2021;
- Philips CA, Theruvath AH, Ravindran R. Toxic hepatitis-associated aplastic anaemia after dual homeopathic remedies and Gymnema sylvestre use. BMJ Case Rep 2022;15(3):e247867. PubMed
Green Tea 219 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Harder S, Fuhr U, Staib AH, Wolff T. Ciprofloxacin-caffeine: a drug interaction established using in vivo and in vitro investigations. Am J Med 1989;87:89S-91S. PubMed
- Carbo M, Segura J, De la Torre R, et al. Effect of quinolones on caffeine disposition. Clin Pharmacol Ther 1989;45:234-40. PubMed
- Healy DP, Polk RE, Kanawati L, et al. Interaction between oral ciprofloxacin and caffeine in normal volunteers. Antimicrob Agents Chemother 1989;33:474-8. PubMed
- Mester R, Toren P, Mizrachi I, et al. Caffeine withdrawal increases lithium blood levels. Biol Psychiatry 1995;37:348-50. PubMed
- Jefferson JW. Lithium tremor and caffeine intake: two cases of drinking less and shaking more. J Clin Psychiatry 1988;49:72-3.
- Mitscher LA, Mitscher LA, Jung M, Shankel D, et al. Chemoprotection: a review of the potential therapeutic antioxidant properties of green tea (Camellia sinensis) and certain of its constituents. Med Res Rev 1997;17:327-65.
- Joeres R, Klinker H, Heusler H, et al. Influence of mexiletine on caffeine elimination. Pharmacol Ther 1987;33:163-9. PubMed
- Vahedi K, Domingo V, Amarenco P, Bousser MG. Ischemic stroke in a sportsman who consumed MaHuang extract and creatine monohydrate for bodybuilding. J Neurol Neurosurg Psychiatr 2000;68:112-3.
- Wakabayashi K, Kono S, Shinchi K, et al. Habitual coffee consumption and blood pressure: A study of self-defense officials in Japan. Eur J Epidemiol 1998;14:669-73. PubMed
- Hodgson JM, Puddey IB, Burke V, et al. Effects on blood pressure of drinking green and black tea. J Hypertens 1999;17:457-63. PubMed
- Booth SL, Madabushi HT, Davidson KW, et al. Tea and coffee brews are not dietary sources of vitamin K-1 (phylloquinone). J Am Diet Assoc 1995;95:82-3. PubMed
- Lou FQ, Zhang MF, Zhang XG, et al. A study on tea-pigment in prevention of atherosclerosis. Chin Med J (Engl) 1989;102:579-83.
- Graham HN. Green tea composition, consumption, and polyphenol chemistry. Prev Med 1992;21:334-50. PubMed
- Rapuri PB, Gallagher JC, Kinyamu HK, Ryschon KL. Caffeine intake increases the rate of bone loss in elderly women and interacts with vitamin D receptor genotypes. Am J Clin Nutr 2001;74:694-700. PubMed
- The National Toxicology Program (NTP). Caffeine. Center for the Evaluation of Risks to Human Reproduction (CERHR). Available at: http://cerhr.niehs.nih.gov/common/caffeine.html.
- Klebanoff MA, Levine RJ, DerSimonian R, et al. Maternal serum paraxanthine, a caffeine metabolite, and the risk of spontaneous abortion. N Engl J Med 1999;341:1639-44. PubMed
- Eskenazi B. Caffeine—filtering the facts. N Engl J Med 1999;341:1688-9. PubMed
- Fernandes O, Sabharwal M, Smiley T, et al. Moderate to heavy caffeine consumption during pregnancy and relationship to spontaneous abortion and abnormal fetal growth: a meta-analysis. Reprod Toxicol 1998;12:435-44. PubMed
- Pollock BG, Wylie M, Stack JA, et al. Inhibition of caffeine metabolism by estrogen replacement therapy in postmenopausal women. J Clin Pharmacol 1999;39:936-40. PubMed
- Dews PB, Curtis GL, Hanford KJ, O'Brien CP. The frequency of caffeine withdrawal in a population-based survey and in a controlled, blinded pilot experiment. J Clin Pharmacol 1999;39:1221-32. PubMed
- FDA. Proposed rule: dietary supplements containing ephedrine alkaloids. Available at: www.verity.fda.gov (Accessed 25 January 2000).
- Weisburger JH. Tea and health: the underlying mechanisms. Proc Soc Exp Biol Med 1999;220:271-5. PubMed
- Taylor JR, Wilt VM. Probable antagonism of warfarin by green tea. Ann Pharmacother 1999;33:426-8. PubMed
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Hagg S, Spigset O, Mjorndal T, Dahlqvist R. Effect of caffeine on clozapine pharmacokinetics in healthy volunteers. Br J Clin Pharmacol 2000;49:59-63. PubMed
- Watson JM, Jenkins EJ, Hamilton P, et al. Influence of caffeine on the frequency and perception of hypoglycemia in free-living patients with type 1 diabetes. Diabetes Care 2000;23:455-9. PubMed
- Lloyd T, Johnson-Rollings N, Eggli DF, et al. Bone status among postmenopausal women with different habitual caffeine intakes: a longitudinal investigation. J Am Coll Nutr 2000;19:256-61. PubMed
- American Academy of Pediatrics. The transfer of drugs and other chemicals into human milk. Pediatrics 2001;108:776-89. PubMed
- Heck AM, DeWitt BA, Lukes AL. Potential interactions between alternative therapies and warfarin. Am J Health Syst Pharm 2000;57:1221-7. DOI
- Sinclair CJ, Geiger JD. Caffeine use in sports. A pharmacological review. J Sports Med Phys Fitness 2000;40:71-9.
- Haller CA, Benowitz NL. Adverse cardiovascular and central nervous system events associated with dietary supplements containing ephedra alkaloids. N Engl J Med 2000;343:1833-8. PubMed
- Ali M, Afzal M. A potent inhibitor of thrombin stimulated platelet thromboxane formation from unprocessed tea. Prostaglandins Leukot Med 1987;27:9-13. PubMed
- Ardlie NG, Glew G, Schultz BG, Schwartz CJ. Inhibition and reversal of platelet aggregation by methyl xanthines. Thromb Diath Haemorrh 1967;18:670-3. DOI
- Ferrini RL, Barrett-Connor E. Caffeine intake and endogenous sex steroid levels in postmenopausal women. The Rancho Bernardo Study. Am J Epidemiol 1996:144:642-4. PubMed
- Pisters KM, Newman RA, Coldman B, et al. Phase I trial of oral green tea extract in adult patients with solid tumors. J Clin Oncol 2001;19:1830-8. PubMed
- Haller CA, Jacob P 3rd, Benowitz NL. Pharmacology of ephedra alkaloids and caffeine after single-dose dietary supplement use. Clin Pharmacol Ther 2002;71:421-32. PubMed
- Bell DG, Jacobs I, Ellerington K. Effect of caffeine and ephedrine ingestion on anaerobic exercise performance. Med Sci Sports Exerc 2001;33:1399-403. PubMed
- Horner NK, Lampe JW. Potential mechanisms of diet therapy for fibrocystic breast conditions show inadequate evidence of effectiveness. J Am Diet Assoc 2000;100:1368-80. PubMed
- Bracken MB, Triche EW, Belanger K, et al. Association of maternal caffeine consumption with decrements in fetal growth. Am J Epidemiol 2003;157:456-66.. PubMed
- McGowan JD, Altman RE, Kanto WP Jr. Neonatal withdrawal symptoms after chronic maternal ingestion of caffeine. South Med J 1988;81:1092-4.. PubMed
- Nehlig A, Debry G. Consequences on the newborn of chronic maternal consumption of coffee during gestation and lactation: a review. J Am Coll Nutr 1994;13:6-21.. PubMed
- Massey LK. Is caffeine a risk factor for bone loss in the elderly? Am J Clin Nutr 2001;74:569-70. PubMed
- Kockler DR, McCarthy MW, Lawson CL. Seizure activity and unresponsiveness after hydroxycut ingestion. Pharmacotherapy 2001;21:647-51.. PubMed
- Nix D, Zelenitsky S, Symonds W, et al. The effect of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. Clin Pharmacol Ther 1992;51:183. DOI
- Ahn WS, Yoo J, Huh SW, et al. Protective effects of green tea extracts (polyphenon E and EGCG) on human cervical lesions. Eur J Cancer Prev 2003;12:383-90. PubMed
- Infante S, Baeza ML, Calvo M, et al. Anaphylaxis due to caffeine. Allergy 2003;58:681-2. PubMed
- Massey LK, Whiting SJ. Caffeine, urinary calcium, calcium metabolism and bone. J Nutr 1993;123:1611-4. PubMed
- Shirai T, Hayakawa H, Akiyama J, et al. Food allergy to green tea. J Allergy Clin Immunol 2003;112:805-6. PubMed
- Jatoi A, Ellison N, Burch PA, et al. A phase II trial of green tea in the treatment of patients with androgen independent metastatic prostate carcinoma. Cancer 2003;97:1442-6.. PubMed
- Nawrot P, Jordan S, Eastwood J, et al. Effects of caffeine on human health. Food Addit Contam 2003;20:1-30. PubMed
- May DC, Jarboe CH, VanBakel AB, Williams WM. Effects of cimetidine on caffeine disposition in smokers and nonsmokers. Clin Pharmacol Ther 1982;31:656-61. PubMed
- Brown NJ, Ryder D, Branch RA. A pharmacodynamic interaction between caffeine and phenylpropanolamine. Clin Pharmacol Ther 1991;50:363-71. PubMed
- Sanderink GJ, Bournique B, Stevens J, et al. Involvement of human CYP1A isoenzymes in the metabolism and drug interactions of riluzole in vitro. Pharmacol Exp Ther 1997;282:1465-72. DOI
- Wahllander A, Paumgartner G. Effect of ketoconazole and terbinafine on the pharmacokinetics of caffeine in healthy volunteers. Eur J Clin Pharmacol 1989;37:279-83. PubMed
- Carrillo JA, Benitez J. Clinically significant pharmacokinetic interactions between dietary caffeine and medications. Clin Pharmacokinet 2000;39:127-53. PubMed
- Underwood DA. Which medications should be held before a pharmacologic or exercise stress test? Cleve Clin J Med 2002;69:449-50. PubMed
- Aqel RA, Zoghbi GJ, Trimm JR, et al. Effect of caffeine administered intravenously on intracoronary-administered adenosine-induced coronary hemodynamics in patients with coronary artery disease. Am J Cardiol 2004;93:343-6. PubMed
- Zheng XM, Williams RC. Serum caffeine levels after 24-hour abstention: clinical implications on dipyridamole (201)Tl myocardial perfusion imaging. J Nucl Med Technol 2002;30:123-7.
- Institute of Medicine. Caffeine for the Sustainment of Mental Task Performance: Formulations for Military Operations. Washington, DC: National Academy Press, 2001. Available at: http://books.nap.edu/books/0309082587/html/index.html. DOI
- Dews PB, O'Brien CP, Bergman J. Caffeine: behavioral effects of withdrawal and related issues. Food Chem Toxicol 2002;40:1257-61. PubMed
- Beach CA, Mays DC, Guiler RC, et al. Inhibition of elimination of caffeine by disulfiram in normal subjects and recovering alcoholics. Clin Pharmacol Ther 1986;39:265-70. PubMed
- Yang YC, Lu FH, Wu JS, et al. The protective effect of habitual tea consumption on hypertension. Arch Intern Med 2004 26;164:1534-40. PubMed
- Son DJ, Cho MR, Jin YR, et al. Antiplatelet effect of green tea catechins: a possible mechanism through arachidonic acid pathway. Prostaglandins Leukot Essent Fatty Acids 2004;71:25-31. PubMed
- Juliano LM, Griffiths RR. A critical review of caffeine withdrawal: empirical validation of symptoms and signs, incidence, severity, and associated features. Psychopharmacology (Berl) 2004;176:1-29. PubMed
- Winkelmayer WC, Stampfer MJ, Willett WC, Curhan GC. Habitual caffeine intake and the risk of hypertension in women. JAMA 2005;294:2330-5. PubMed
- Raaska K, Raitasuo V, Laitila J, Neuvonen PJ. Effect of caffeine-containing versus decaffeinated coffee on serum clozapine concentrations in hospitalised patients. Basic Clin Pharmacol Toxicol 2004;94:13-8. DOI
- Forrest WH Jr, Bellville JW, Brown BW Jr. The interaction of caffeine with pentobarbital as a nighttime hypnotic. Anesthesiology 1972;36:37-41. PubMed
- Lake CR, Rosenberg DB, Gallant S, et al. Phenylpropanolamine increases plasma caffeine levels. Clin Pharmacol Ther 1990;47:675-85. PubMed
- Bonkovsky HL. Hepatotoxicity associated with supplements containing Chinese green tea (Camellia sinensis). Ann Intern Med 2006;144:68-71.
- Gloro R, Hourmand-Ollivier I, Mosquet B, et al. Fulminant hepatitis during self-medication with hydroalcoholic extract of green tea. Eur J Gastroenterol Hepatol 2005;17:1135-7. PubMed
- Donovan JL, Chavin KD, Devane CL, et al. Green tea (Camellia sinensis) extract does not alter cytochrome P450 3A4 or 2D6 activity in healthy volunteers. Drug Metab Dispos 2004;32:906-8. PubMed
- Chu KO, Wang CC, Chu CY, et al. Pharmacokinetic studies of green tea catechins in maternal plasma and fetuses in rats. J Pharm Sci 2006;95:1372-81. PubMed
- Isbrucker RA, Edwards JA, Wolz E, et al. Safety studies on epigallocatechin gallate (EGCG) preparations. Part 3: teratogenicity and reproductive toxicity studies in rats. Food Chem Toxicol 2006;44:651-61. PubMed
- Navarro-Peran E, Cabezas-Herrera J, Garcia-Canovas F, et al. The antifolate activity of tea catechins. Cancer Res 2005;65:2059-64. PubMed
- Jimenez-Saenz M, Martinez-Sanchez, MDC. Acute hepatitis associated with the use of green tea infusions. J Hepatol 2006;44:616-9. PubMed
- Bradley Pharmaceuticals. Veregen Prescribing Information. October 2006.
- Correa A, Stolley A, Liu Y. Prenatal tea consumption and risks of anencephaly and spina bifida. Ann Epidemiol 2000;10:476-7. PubMed
- Weng X, Odouli R, Li DK. Maternal caffeine consumption during pregnancy and the risk of miscarriage: a prospective cohort study. Am J Obstet Gynecol 2008;198:279.e1-8. PubMed
- Savitz DA, Chan RL, Herring AH, et al. Caffeine and miscarriage risk. Epidemiology 2008;19:55-62. PubMed
- Golden ED, Lam PY, Kardosh A, et al. Green tea polyphenols block the anticancer effects of bortezomib and other boronic acid-based proteasome inhibitors. Blood 2009;113:5927-37. PubMed
- Misaka S, Yatabe J, Muller F, et al. Green Tea Ingestion Greatly Reduces Plasma Concentrations of Nadolol in Healthy Subjects. Clin Pharmacol Ther 2014. [Epub ahead of print]. PubMed
- Roth M, Timmermann BN, Hagenbuch B. Interactions of green tea catechins with organic anion-transporting polypeptides. Drug Metab Dispos 2011;39:920-6. PubMed
- Kato Y, Miyazaki T, Kano T, et al. Involvement of influx and efflux transport systems in gastrointestinal absorption of celiprolol. J Pharm Sci 2009;98:2529-39. PubMed
- Chan, H. T., So, L. T., Li, S. W., Siu, C. W., Lau, C. P., and Tse, H. F. Effect of herbal consumption on time in therapeutic range of warfarin therapy in patients with atrial fibrillation. J.Cardiovasc.Pharmacol. 2011;58(1):87-90. PubMed
- Nishikawa, M., Ariyoshi, N., Kotani, A., Ishii, I., Nakamura, H., Nakasa, H., Ida, M., Nakamura, H., Kimura, N., Kimura, M., Hasegawa, A., Kusu, F., Ohmori, S., Nakazawa, K., and Kitada, M. Effects of continuous ingestion of green tea or grape seed extrac
- Shet, M. S., McPhaul, M., Fisher, C. W., Stallings, N. R., and Estabrook, R. W. Metabolism of the antiandrogenic drug (Flutamide) by human CYP1A2. Drug Metab Dispos. 1997;25(11):1298-1303.
- Staib, A. H., Stille, W., Dietlein, G., Shah, P. M., Harder, S., Mieke, S., and Beer, C. Interaction between quinolones and caffeine. Drugs 1987;34 Suppl 1:170-174. PubMed
- Stille, W., Harder, S., Mieke, S., Beer, C., Shah, P. M., Frech, K., and Staib, A. H. Decrease of caffeine elimination in man during co-administration of 4-quinolones. J.Antimicrob.Chemother. 1987;20(5):729-734. PubMed
- Fuhr, U., Strobl, G., Manaut, F., Anders, E. M., Sorgel, F., Lopez-de-Brinas, E., Chu, D. T., Pernet, A. G., Mahr, G., Sanz, F., and . Quinolone antibacterial agents: relationship between structure and in vitro inhibition of the human cytochrome P450 isof
- Kot, M. and Daniel, W. A. Effect of diethyldithiocarbamate (DDC) and ticlopidine on CYP1A2 activity and caffeine metabolism: an in vitro comparative study with human cDNA-expressed CYP1A2 and liver microsomes. Pharmacol Rep. 2009;61(6):1216-1220. PubMed
- Gasior, M., Borowicz, K., Buszewicz, G., Kleinrok, Z., and Czuczwar, S. J. Anticonvulsant activity of phenobarbital and valproate against maximal electroshock in mice during chronic treatment with caffeine and caffeine discontinuation. Epilepsia 1996;37(3 PubMed
- Jankiewicz, K., Chroscinska-Krawczyk, M., Blaszczyk, B., and Czuczwar, S. J. [Caffeine and antiepileptic drugs: experimental and clinical data]. Przegl.Lek. 2007;64(11):965-967.
- Luszczki, J. J., Zuchora, M., Sawicka, K. M., Kozinska, J., and Czuczwar, S. J. Acute exposure to caffeine decreases the anticonvulsant action of ethosuximide, but not that of clonazepam, phenobarbital and valproate against pentetrazole-induced seizures i
- Chroscinska-Krawczyk, M., Jargiello-Baszak, M., Walek, M., Tylus, B., and Czuczwar, S. J. Caffeine and the anticonvulsant potency of antiepileptic drugs: experimental and clinical data. Pharmacol.Rep. 2011;63(1):12-18. PubMed
- Vaz, J., Kulkarni, C., David, J., and Joseph, T. Influence of caffeine on pharmacokinetic profile of sodium valproate and carbamazepine in normal human volunteers. Indian J.Exp.Biol. 1998;36(1):112-114.
- Gasior, M., Swiader, M., Przybylko, M., Borowicz, K., Turski, W. A., Kleinrok, Z., and Czuczwar, S. J. Felbamate demonstrates low propensity for interaction with methylxanthines and Ca2+ channel modulators against experimental seizures in mice. Eur.J Phar PubMed
- Mohiuddin, M., Azam, A. T., Amran, M. S., and Hossain, M. A. In vive effects of gliclazide and metformin on the plasma concentration of caffeine in healthy rats. Pak.J Biol Sci 5-1-2009;12(9):734-737.
- Mays, D. C., Camisa, C., Cheney, P., Pacula, C. M., Nawoot, S., and Gerber, N. Methoxsalen is a potent inhibitor of the metabolism of caffeine in humans. Clin.Pharmacol.Ther. 1987;42(6):621-626. PubMed
- Wojcikowski, J. and Daniel, W. A. Perazine at therapeutic drug concentrations inhibits human cytochrome P450 isoenzyme 1A2 (CYP1A2) and caffeine metabolism--an in vitro study. Pharmacol Rep. 2009;61(5):851-858. PubMed
- Daniel, W. A., Syrek, M., Rylko, Z., and Kot, M. Effects of phenothiazine neuroleptics on the rate of caffeine demethylation and hydroxylation in the rat liver. Pol.J Pharmacol 2001;53(6):615-621.
- Norager, C. B., Jensen, M. B., Weimann, A., and Madsen, M. R. Metabolic effects of caffeine ingestion and physical work in 75-year old citizens. A randomized, double-blind, placebo-controlled, cross-over study. Clin Endocrinol (Oxf) 2006;65(2):223-228. PubMed
- Wang, X. and Yeung, J. H. Effects of the aqueous extract from Salvia miltiorrhiza Bunge on caffeine pharmacokinetics and liver microsomal CYP1A2 activity in humans and rats. J Pharm Pharmacol 2010;62(8):1077-1083.
- Kot M, Daniel WA. Caffeine as a marker substrate for testing cytochrome P450 activity in human and rat. Pharmacol Rep 2008;60:789-97.
- Kjaerstad MB, Nielsen F, Nohr-Jensen L, et al. Systemic uptake of miconazole during vaginal suppository use and effect on CYP1A2 and CYP3A4 associated enzyme activities in women. Eur J Clin Pharmacol 2010;66:1189-97. PubMed
- Goh BC, Reddy NJ, Dandamudi UB, et al. An evaluation of the drug interaction potential of pazopanib, an oral vascular endothelial growth factor receptor tyrosine kinase inhibitor, using a modified Cooperstown 5+1 cocktail in patients with advanced solid t
- Chen Y, Kang Z, Yan J, et al. Liu wei di huang wan, a well-known traditional Chinese medicine induces CYP1A2 while suppressing CYP2A6 and N-acetyltransferase 2 acivities in man. J Ethnopharmacol 2010;132:213-8.
- Suzuki S, Murayama Y, Sugiyama E, et al. Estimating pediatric doses of drugs metabolized by cytochrome P450 (CYP) isozymes, based on physiological liver development and serum protein levels. Yakugaku Zasshi 2010;130:613-20. PubMed
- Chien CF, Wu YT, Lee WC, et al. Herb-drug interaction of Andrographis paniculata extract and andrographolide on the pharmacokinetics of theophylline in rats. Chem Biol Interact 2010;184:458-65. PubMed
- Mills BM, Zaya MJ, Walters RR, et al. Current cytochrome P450 phenotyping methods applied to metabolic drug -drug interaction prediction in dogs. Drug Metab Dispos 2010;38:396-404. PubMed
- Turpault S, Brian W, Van Horn R, et al. Pharmacokinetic assessment of a five-probe cocktail for CYPs 1A2, 2C9, 2C19, 2D6, and 3A. Br J Clin Pharmacol 2009;68:928-35. PubMed
- Filimonova AA, Ziganshina LE, Ziganshin AU, Chichirov AA. On the possibility of patient phenotyping on the basis of cytochrome p-450 1A2 isoenzyme activity using caffeine as the test substrate. Eksp Klin Farmakol 2009;72:61-5.
- Jenkins J, Williams D, Deng Y, et al. Eltrombopag, an oral thrombopoietin receptor agonist, has no impact on the pharmacokinetic profile of probe drugs for cytochrome P450 isoenzymes CYP3A4, CYP1A2, CYP2C9 and CYP2C19 in healthy men: a cocktail analysis.
- Chow, H. H., Cai, Y., Hakim, I. A., Crowell, J. A., Shahi, F., Brooks, C. A., Dorr, R. T., Hara, Y., and Alberts, D. S. Pharmacokinetics and safety of green tea polyphenols after multiple-dose administration of epigallocatechin gallate and polyphenon E i
- Gross, G., Meyer, K. G., Pres, H., Thielert, C., Tawfik, H., and Mescheder, A. A randomized, double-blind, four-arm parallel-group, placebo-controlled Phase II/III study to investigate the clinical efficacy of two galenic formulations of Polyphenon E in
- Stockfleth, E., Beti, H., Orasan, R., Grigorian, F., Mescheder, A., Tawfik, H., and Thielert, C. Topical Polyphenon E in the treatment of external genital and perianal warts: a randomized controlled trial. Br.J Dermatol. 2008;158(6):1329-1338.
- Smits, P., Temme, L., and Thien, T. The cardiovascular interaction between caffeine and nicotine in humans. Clin Pharmacol Ther 1993;54(2):194-204. PubMed
- MacKenzie, T., Comi, R., Sluss, P., Keisari, R., Manwar, S., Kim, J., Larson, R., and Baron, J. A. Metabolic and hormonal effects of caffeine: randomized, double-blind, placebo-controlled crossover trial. Metabolism 2007;56(12):1694-1698. PubMed
- Lopez-Garcia, E., Rodriguez-Artalejo, F., Rexrode, K. M., Logroscino, G., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of stroke in women. Circulation 3-3-2009;119(8):1116-1123. PubMed
- Zhang, W., Lopez-Garcia, E., Li, T. Y., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of cardiovascular diseases and all-cause mortality among men with type 2 diabetes. Diabetes Care 2009;32(6):1043-1045. PubMed
- Moisey, L. L., Robinson, L. E., and Graham, T. E. Consumption of caffeinated coffee and a high carbohydrate meal affects postprandial metabolism of a subsequent oral glucose tolerance test in young, healthy males. Br.J Nutr. 2010;103(6):833-841. PubMed
- Chroscinska-Krawczyk, M., Ratnaraj, N., Patsalos, P. N., and Czuczwar, S. J. Effect of caffeine on the anticonvulsant effects of oxcarbazepine, lamotrigine and tiagabine in a mouse model of generalized tonic-clonic seizures. Pharmacol Rep. 2009;61(5):819 PubMed
- Simmonds, M. J., Minahan, C. L., and Sabapathy, S. Caffeine improves supramaximal cycling but not the rate of anaerobic energy release. Eur.J Appl Physiol 2010;109(2):287-295. PubMed
- Buscemi, S., Verga, S., Batsis, J. A., Donatelli, M., Tranchina, M. R., Belmonte, S., Mattina, A., Re, A., and Cerasola, G. Acute effects of coffee on endothelial function in healthy subjects. Eur.J Clin Nutr. 2010;64(5):483-489. PubMed
- Rigato, I., Blarasin, L., and Kette, F. Severe hypokalemia in 2 young bicycle riders due to massive caffeine intake. Clin J Sport Med. 2010;20(2):128-130. PubMed
- Ernest, D., Chia, M., and Corallo, C. E. Profound hypokalaemia due to Nurofen Plus and Red Bull misuse. Crit Care Resusc. 2010;12(2):109-110. DOI
- Conen, D., Chiuve, S. E., Everett, B. M., Zhang, S. M., Buring, J. E., and Albert, C. M. Caffeine consumption and incident atrial fibrillation in women. Am J Clin Nutr 2010;92(3):509-514. PubMed
- Reis, J. P., Loria, C. M., Steffen, L. M., Zhou, X., van, Horn L., Siscovick, D. S., Jacobs, D. R., Jr., and Carr, J. J. Coffee, decaffeinated coffee, caffeine, and tea consumption in young adulthood and atherosclerosis later in life: the CARDIA study. A PubMed
- Clausen, T. Hormonal and pharmacological modification of plasma potassium homeostasis. Fundam.Clin Pharmacol 2010;24(5):595-605. PubMed
- Gronroos, N. N. and Alonso, A. Diet and risk of atrial fibrillation - epidemiologic and clinical evidence -. Circ.J 2010;74(10):2029-2038. PubMed
- Perera, V., Gross, A. S., and McLachlan, A. J. Caffeine and paraxanthine HPLC assay for CYP1A2 phenotype assessment using saliva and plasma. Biomed.Chromatogr. 2010;24(10):1136-1144. PubMed
- Orozco-Gregorio, H., Mota-Rojas, D., Bonilla-Jaime, H., Trujillo-Ortega, M. E., Becerril-Herrera, M., Hernandez-Gonzalez, R., and Villanueva-Garcia, D. Effects of administration of caffeine on metabolic variables in neonatal pigs with peripartum asphyxia PubMed
- Izzo, A. A. and Ernst, E. Interactions between herbal medicines and prescribed drugs: an updated systematic review. Drugs 2009;69(13):1777-1798. PubMed
- Laurie, S. A., Miller, V. A., Grant, S. C., Kris, M. G., and Ng, K. K. Phase I study of green tea extract in patients with advanced lung cancer. Cancer Chemother.Pharmacol. 2005;55(1):33-38. PubMed
- Chiu, A. E., Chan, J. L., Kern, D. G., Kohler, S., Rehmus, W. E., and Kimball, A. B. Double-blinded, placebo-controlled trial of green tea extracts in the clinical and histologic appearance of photoaging skin. Dermatol Surg. 2005;31(7 Pt 2):855-860. PubMed
- Javaid, A. and Bonkovsky, H. L. Hepatotoxicity due to extracts of Chinese green tea (Camellia sinensis): a growing concern. J Hepatol 2006;45(2):334-335. PubMed
- Martinez-Sierra, C., Rendon, Unceta P., and Martin, Herrera L. [Acute hepatitis after green tea ingestion]. Med Clin (Barc.) 6-17-2006;127(3):119.
- Molinari, M., Watt, K. D., Kruszyna, T., Nelson, R., Walsh, M., Huang, W. Y., Nashan, B., and Peltekian, K. Acute liver failure induced by green tea extracts: case report and review of the literature. Liver Transpl. 2006;12(12):1892-1895. PubMed
- Chow, H. H., Hakim, I. A., Vining, D. R., Crowell, J. A., Cordova, C. A., Chew, W. M., Xu, M. J., Hsu, C. H., Ranger-Moore, J., and Alberts, D. S. Effects of repeated green tea catechin administration on human cytochrome P450 activity. Cancer Epidemiol.B PubMed
- Federico, A., Tiso, A., and Loguercio, C. A case of hepatotoxicity caused by green tea. Free Radic.Biol Med 8-1-2007;43(3):474. PubMed
- Sarma, D. N., Barrett, M. L., Chavez, M. L., Gardiner, P., Ko, R., Mahady, G. B., Marles, R. J., Pellicore, L. S., Giancaspro, G. I., and Low, Dog T. Safety of green tea extracts : a systematic review by the US Pharmacopeia. Drug Saf 2008;31(6):469-484. PubMed
- Engdal, S. and Nilsen, O. G. In vitro inhibition of CYP3A4 by herbal remedies frequently used by cancer patients. Phytother.Res. 2009;23(7):906-912.
- Bergman, J. and Schjott, J. Hepatitis caused by Lotus-f3? Basic Clin Pharmacol.Toxicol. 2009;104(5):414-416. PubMed
- Kalus, U., Kiesewetter, H., and Radtke, H. Effect of CYSTUS052 and green tea on subjective symptoms in patients with infection of the upper respiratory tract. Phytother.Res. 2010;24(1):96-100.
- Tatti, S., Stockfleth, E., Beutner, K. R., Tawfik, H., Elsasser, U., Weyrauch, P., and Mescheder, A. Polyphenon E: a new treatment for external anogenital warts. Br.J Dermatol. 2010;162(1):176-184.
- Tsao, A. S., Liu, D., Martin, J., Tang, X. M., Lee, J. J., El-Naggar, A. K., Wistuba, I., Culotta, K. S., Mao, L., Gillenwater, A., Sagesaka, Y. M., Hong, W. K., and Papadimitrakopoulou, V. Phase II randomized, placebo-controlled trial of green tea extra
- Liatsos, G. D., Moulakakis, A., Ketikoglou, I., and Klonari, S. Possible green tea-induced thrombotic thrombocytopenic purpura. Am.J Health Syst.Pharm. 4-1-2010;67(7):531-534. PubMed
- Josic, J., Olsson, A. T., Wickeberg, J., Lindstedt, S., and Hlebowicz, J. Does green tea affect postprandial glucose, insulin and satiety in healthy subjects: a randomized controlled trial. Nutr.J. 2010;9:63. PubMed
- Miller, R. J., Jackson, K. G., Dadd, T., Mayes, A. E., Brown, A. L., and Minihane, A. M. The impact of the catechol-O-methyltransferase genotype on the acute responsiveness of vascular reactivity to a green tea extract. Br.J.Nutr. 2011;105(8):1138-1144.
- Rohde, J., Jacobsen, C., and Kromann-Andersen, H. [Toxic hepatitis triggered by green tea]. Ugeskr.Laeger 1-17-2011;173(3):205-206.
- Tzellos, T. G., Sardeli, C., Lallas, A., Papazisis, G., Chourdakis, M., and Kouvelas, D. Efficacy, safety and tolerability of green tea catechins in the treatment of external anogenital warts: a systematic review and meta-analysis. J.Eur.Acad.Dermatol.Ve PubMed
- Otera, H., Tada, K., Sakurai, T., Hashimoto, K., and Ikeda, A. Hypersensitivity pneumonitis associated with inhalation of catechin-rich green tea extracts. Respiration 2011;82(4):388-392. PubMed
- Yellapu, R. K., Mittal, V., Grewal, P., Fiel, M., and Schiano, T. Acute liver failure caused by 'fat burners' and dietary supplements: a case report and literature review. Can.J.Gastroenterol. 2011;25(3):157-160. PubMed
- Karth, A., Holoshitz, N., Kavinsky, C. J., Trohman, R., and McBride, B. F. A case report of atrial fibrillation potentially induced by hydroxycut: a multicomponent dietary weight loss supplement devoid of sympathomimetic amines. J.Pharm.Pract. 2010;23(3) PubMed
- Hsu, C. H., Liao, Y. L., Lin, S. C., Tsai, T. H., Huang, C. J., and Chou, P. Does supplementation with green tea extract improve insulin resistance in obese type 2 diabetics? A randomized, double-blind, and placebo-controlled clinical trial. Altern.Med.R
- Zheng XX, Xu YL, Li SH, et al. Green tea intake lowers fasting serum total and LDL cholesterol in adults: a meta-analysis of 14 randomized controlled trials. Am.J.Clin.Nutr. 2011;94:601-610. PubMed
- Miller, R. J., Jackson, K. G., Dadd, T., Mayes, A. E., Brown, A. L., Lovegrove, J. A., and Minihane, A. M. The impact of the catechol-O-methyltransferase genotype on vascular function and blood pressure after acute green tea ingestion. Mol.Nutr.Food Res.
- Bogdanski, P., Suliburska, J., Szulinska, M., Stepien, M., Pupek-Musialik, D., and Jablecka, A. Green tea extract reduces blood pressure, inflammatory biomarkers, and oxidative stress and improves parameters associated with insulin resistance in obese, h
- Jurgens, T. M., Whelan, A. M., Killian, L., Doucette, S., Kirk, S., and Foy, E. Green tea for weight loss and weight maintenance in overweight or obese adults. Cochrane.Database.Syst.Rev. 2012;12:CD008650. PubMed
- Sakamoto, O., Saita, N., Yamasaki, H., Tamanoi, M., and Ando, M. Pulmonary granulomatosis caused by aspirated green tea. Chest 1994;106(1):308-309. PubMed
- Jiménez-Encarnación E, Ríos G, Muñoz-Mirabal A, Vilá LM. Euforia-induced acute hepatitis in a patient with scleroderma. BMJ Case Rep 2012;2012. PubMed
- Choi JS, Burm JP. Effects of oral epigallocatechin gallate on the pharmacokinetics of nicardipine in rats. Arch Pharm Res. 2009 Dec;32(12):1721-5. PubMed
- Chung JH, Choi DH, Choi JS. Effects of oral epigallocatechin gallate on the oral pharmacokinetics of verapamil in rats. Biopharm Drug Dispos. 2009 Mar;30(2):90-3. PubMed
- Crew KD, Brown P, Greenlee H, Bevers TB, Arun B, Hudis C, McArthur HL, Chang J, Rimawi M, Vornik L, Cornelison TL, Wang A, Hibshoosh H, Ahmed A, Terry MB, Santella RM, Lippman SM, Hershman DL. Phase IB randomized, double-blinded, placebo-controlled, dose
- Dryden GW, Lam A, Beatty K, Qazzaz HH, McClain CJ. A pilot study to evaluate the safety and efficacy of an oral dose of (-)-epigallocatechin-3-gallate-rich polyphenon E in patients with mild to moderate ulcerative colitis. Inflamm Bowel Dis. 2013 Aug;19(9 PubMed
- Gallo E, Maggini V, Berardi M, Pugi A, Notaro R, Talini G, Vannozzi G, Bagnoli S, Forte P, Mugelli A, Annese V, Firenzuoli F, Vannacci A. Is green tea a potential trigger for autoimmune hepatitis? Phytomedicine. 2013 Oct 15;20(13):1186-9. PubMed
- Liu K, Zhou R, Wang B, Chen K, Shi LY, Zhu JD, Mi MT. Effect of green tea on glucose control and insulin sensitivity: a meta-analysis of 17 randomized controlled trials. Am J Clin Nutr. 2013 Aug;98(2):340-8. PubMed
- Onakpoya I, Spencer E, Heneghan C, Thompson M. The effect of green tea on blood pressure and lipid profile: a systematic review and meta-analysis of randomized clinical trials. Nutr Metab Cardiovasc Dis. 2014 Aug;24:823-36. PubMed
- Patel SS, Beer S, Kearney DL, Phillips G, Carter BA. Green tea extract: a potential cause of acute liver failure. World J Gastroenterol. 2013 Aug 21;19(31):5174-7. PubMed
- Pillukat MH, Bester C, Hensel A, Lechtenberg M, Petereit F, Beckebaum S, Müller KM, Schmidt HH. Concentrated green tea extract induces severe acute hepatitis in a 63-year-old woman--a case report with pharmaceutical analysis. J Ethnopharmacol. 2014 Aug 8; PubMed
- Schönthal AH. Adverse effects of concentrated green tea extracts. Mol Nutr Food Res. 2011 Jun;55(6):874-85. PubMed
- Shiraishi M, Haruna M, Matsuzaki M, Ota E, Murayama R, Murashima S. Association between the serum folate levels and tea consumption during pregnancy. Biosci Trends. 2010 Oct;4(5):225-30.
- Jang EH, Choi JY, Park CS, Lee SK, Kim CE, Park HJ, Kang JS, Lee JW, Kang JH. Effects of green tea extract administration on the pharmacokinetics of clozapine in rats. J Pharm Pharmacol. 2005 Mar;57(3):311-6. PubMed
- Trudel D, Labbé DP, Araya-Farias M, Doyen A, Bazinet L, Duchesne T, Plante M, Grégoire J, Renaud MC, Bachvarov D, Têtu B, Bairati I. A two-stage, single-arm, phase II study of EGCG-enriched green tea drink as a maintenance therapy in women with advanced s
- Zheng XX, Xu YL, Li SH, Hui R, Wu YJ, Huang XH. Effects of green tea catechins with or without caffeine on glycemic control in adults: a meta-analysis of randomized controlled trials. Am J Clin Nutr. 2013 Apr;97(4):750-62. PubMed
- Caldeira D, Martins C, Alves LB, Pereira H, Ferreira JJ, Costa J. Caffeine does not increase the risk of atrial fibrillation: a systematic review and meta-analysis of observational studies. Heart. 2013;99(19):1383-9. doi: 10.1136/heartjnl-2013-303950. Re PubMed
- Cheng M, Hu Z, Lu X, Huang J, Gu D. Caffeine intake and atrial fibrillation incidence: dose response meta-analysis of prospective cohort studies. Can J Cardiol. 2014 Apr;30(4):448-54. doi: 10.1016/j.cjca.2013.12.026. Epub 2014 2. Review. PubMed
- van der Hoeven N, Visser I, Schene A, van den Born BJ. Severe hypertension related to caffeinated coffee and tranylcypromine: a case report. Ann Intern Med. 2014 May 6;160(9):657-8. doi: 10.7326/L14-5009-8. No abstract available. PubMed
- Dixit S, Stein PK, Dewland TA, Dukes JW, Vittinghoff E, Heckbert SR, Marcus GM. Consumption of Caffeinated Products and Cardiac Ectopy. J Am Heart Assoc. 2016 26;5(1). pii: e002503. doi: 10.1161/JAHA.115.002503. PubMed
- Health Canada. Health Product Info Watch. October 2016; 5-6. Available at: http://www.hc-sc.gc.ca/dhp-mps/medeff/bulletin/hpiw-ivps_2016-10-eng.php#a15.
- Green Tea Extract-Containing Natural Health Products - Rare Risk of Serious Liver Injury. Recalls & alerts. November 15, 2017. http://healthycanadians.gc.ca/recall-alert-rappel-avis/hc-sc/2017/65100a-eng.php. Accessed November 10, 2017.
- Mazzanti G, Di Sotto A, Vitalone A. Hepatotoxicity of green tea: an update. Arch Toxicol. 2015;89(8):1175-91. PubMed
- Isomura T, Suzuki S, Origasa H, et al. Liver-related safety assessment of green tea extracts in humans: a systematic review of randomized controlled trials. Eur J Clin Nutr. 2016;70(11):1221-1229. PubMed
- Drug Record: Green Tea (Camellia Sinesis). LiverTox: National Institutes of Health, U.S. Department of Health & Human Services, March 2014. https://livertox.nlm.nih.gov//GreenTea.htm. Accessed November 20, 2017.
- Yates AA, Erdman JW Jr, Shao A, Dolan LC, Griffiths JC. Bioactive nutrients - Time for tolerable upper intake levels to address safety. Regul Toxicol Pharmacol. 2017;84:94-101. PubMed
- Younes M, Aggett P, Aguilar F, et al. EFSA Panel on Food Additives and Nutrient Sources added to Food (ANS). Scientific opinion on the safety of green tea catechins. EFSA Journal 2018;16(4):5239. PubMed
- Zuchinali P, Riberio PA, Pimentel M, da Rosa PR, Zimerman LI, Rohde LE. Effect of caffeine on ventricular arrhythmia: a systematic review and meta-analysis of experimental and clinical studies. Europace 2016 Feb;18(2):257-66. PubMed
- Dostal AM, Samavat H, Bedell S, et al. The safety of green tea extract supplementation in postmenopausal women at risk for breast cancer: results of the Minnesota Green Tea Trial. Food Chem Toxicol. 2015 Sep;83:26-35. PubMed
- Shamekhi Z, Amani R, Habibagahi Z, Namjoyan F, Ghadiri A, Saki Malehi A. A Randomized, Double-blind, Placebo-controlled Clinical Trial Examining the Effects of Green Tea Extract on Systemic Lupus Erythematosus Disease Activity and Quality of Life. Phytoth PubMed
- Lagier D, Nee L, Guieu R, et al. Peri-operative oral caffeine does not prevent postoperative atrial fibrillation after heart valve surgery with cardiopulmonary bypass: a randomized controlled clinical trial. Eur J Anaesthesiol. 2018 Apr 26. [Epub ahead of DOI
- Voskoboinik A, Kalman JM, Kistler PM. Caffeine and arrhythmias: time to grind the data. JACC: Clin Electrophysiol. 2018;4(4):425-32. PubMed
- Chong SJ, Howard KA, Knox C. Hypokalaemia and drinking green tea: a literature review and report of 2 cases. BMJ Case Rep. 2016;2016. pii: bcr2016214425. PubMed
- Qiao J, Gu C, Shang W, et al. Effect of green tea on pharmacokinetics of 5-fluorouracil in rats and pharmacodynamics in human cell lines in vitro. Food Chem Toxicol. 2011;49(6):1410-5. PubMed
- Abe O, Ono T, Sato H, et al. Role of (-)-epigallocatechin gallate in the pharmacokinetic interaction between nadolol and green tea in healthy volunteers. Eur J Clin Pharmacol 2018;74(6):775-83. doi: 10.1007/s00228-018-2436-2. PubMed
- Wikoff D, Welsh BT, Henderson R, et al. Systematic review of the potential adverse effects of caffeine consumption in healthy adults, pregnant women, adolescents, and children. Food Chem Toxicol 2017;109:585-648. PubMed
- Nutescu EA, Shapiro NL, Ibrahim S, et al. Warfarin and its interactions with foods, herbs and other dietary supplements. Expert Opin Drug Saf. 2006;5(3):433-51. PubMed
- Abdelkawy KS, Abdelaziz RM, Abdelmageed AM, Donia AM, El-Khodary NM. Effects of green tea extract on atorvastatin pharmacokinetics in healthy volunteers. Eur J Drug Metab Pharmacokinet. 2020;45(3):351-360. PubMed
- Filippini T, Malavolti M, Borrelli F, et al. Green tea (Camellia sinensis) for the prevention of cancer. Cochrane Database Syst Rev. 2020;3(3):CD005004. PubMed
- Huang S, Xu Q, Liu L, et al. Effect of green tea and (-)-epigallocatechin gallate on the pharmacokinetics of rosuvastatin. Curr Drug Metab. 2020. PubMed
- Mahmoodi M, Hosseini R, Kazemi A, Ofori-Asenso R, Mazidi M, Mazloomi SM. Effects of green tea or green tea catechin on liver enzymes in healthy individuals and people with nonalcoholic fatty liver disease: A systematic review and meta-analysis of randomiz
- Misaka S, Abe O, Ono T, et al. Effects of single green tea ingestion on pharmacokinetics of nadolol in healthy volunteers. Br J Clin Pharmacol. 2020. PubMed
- Oketch-Rabah HA, Roe AL, Rider CV, et al. United States Pharmacopeia (USP) comprehensive review of the hepatotoxicity of green tea extracts. Toxicol Rep. 2020;7:386-402. PubMed
- Kim TE, Ha N, Kim Y, et al. Effect of epigallocatechin-3-gallate, major ingredient of green tea, on the pharmacokinetics of rosuvastatin in healthy volunteers. Drug Des Devel Ther. 2017;11:1409-1416. PubMed
- Misaka S, Ono Y, Uchida A, et al. Impact of green tea catechin ingestion on the pharmacokinetics of lisinopril in healthy volunteers. Clin Transl Sci. 2020. PubMed
- Darweesh RS, El-Elimat T, Zayed A, et al. The effect of grape seed and green tea extracts on the pharmacokinetics of imatinib and its main metabolite, N-desmethyl imatinib, in rats. BMC Pharmacol Toxicol. 2020;21(1):77. PubMed
- Sonoda J, Ogata K, Yoshikawa N, Sato K, Ikeda R, Shimodozono Y. Impact of green tea intake on the pharmacokinetics of celiprolol in healthy subjects. Int J Clin Pharmacol Ther. 2020. PubMed
- Kim S, Park TH, Kim WI, Park S, Kim JH, Cho MK. The effects of green tea on acne vulgaris: A systematic review and meta-analysis of randomized clinical trials. Phytother Res. 2021;35(1):374-383. PubMed
- Percevault S, Charpiat B, Lebossé F, Mabrut JY, Vial T, Colom M. Green tea and hepatoxicity: Two case reports. Therapie 2021. PubMed
- Kajita N, Miyama S, Kinoshita K, Yoshida K, Narita M. Green tea-induced anaphylaxis: The first pediatric case report. Allergol Int 2021;70(4):507-508. PubMed
- Zheng KH, Zhu K, Wactawski-Wende J, et al. Caffeine intake from coffee and tea and invasive breast cancer incidence among postmenopausal women in the Women's Health Initiative. Int J Cancer 2021;149(12):2032-2044. PubMed
- Wang S, Li X, Yang Y, et al. Does coffee, tea and caffeine consumption reduce the risk of incident breast cancer? A systematic review and network meta-analysis. Public Health Nutr 2021;24(18):6377-6389. PubMed
- Alshabi AM, Alkahtani SA, Shaikh IA, Habeeb MS. Caffeine modulates pharmacokinetic and pharmacodynamic profiles of pioglitazone in diabetic rats: Impact on therapeutics. Saudi Med J 2021;42(2):151-160. PubMed
- Gleason JL, Sundaram R, Mitro SD, et al. Association of maternal caffeine consumption during pregnancy with child growth. JAMA Netw Open. 2022;5(10):e2239609. PubMed
- Seufferlein T, Ettrich TJ, Menzler S, et al. Green tea extract to prevent colorectal adenomas, results of a randomized, placebo-controlled clinical trial. Am J Gastroenterol 2022;117(6):884-894. PubMed
- Teramoto M, Yamagishi K, Muraki I, Tamakoshi A, Iso H. Coffee and green tea consumption and cardiovascular disease mortality among people with and without hypertension. J Am Heart Assoc 2023;12(2):e026477. PubMed
- Veerman GDM, van der Werff SC, Koolen SLW, et al. The influence of green tea extract on nintedanib's bioavailability in patients with pulmonary fibrosis. Biomed Pharmacother 2022;151:113101. PubMed
- Misaka S, Ono Y, Taudte RV, et al. Exposure of fexofenadine, but not pseudoephedrine, is markedly decreased by green tea extract in healthy volunteers. Clin Pharmacol Ther 2022;112(3):627-634. PubMed
- Zhao H, Zhu W, Zhao X, et al. Efficacy of epigallocatechin-3-gallate in preventing dermatitis in patients with breast cancer receiving postoperative radiotherapy: A double-blind, placebo-controlled, phase 2 randomized clinical trial. JAMA Dermatol 2022;15 PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
Turmeric 102 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Sharma RA, McLelland HR, Hill KA, et al. Pharmacodynamic and pharmacokinetic study of oral Curcuma extract in patients with colorectal cancer. Clin Cancer Res 2001;7:1894-900..
- Shah BH, Nawaz Z, Pertani SA. Inhibitory effect of curcumin, a food spice from turmeric, on platelet-activating factor- and arachidonic acid-mediated platelet aggregation through inhibition of thromboxane formation and Ca2+ signaling. Biochem Pharmacol 1 PubMed
- Hata M, Sasaki E, Ota M, et al . Allergic contact dermatitis from curcumin (turmeric). Contact Dermatitis 1997;36:107-8. PubMed
- Kuttan R, Sudheeran PC, Josph CD. Turmeric and curcumin as topical agents in cancer therapy. Tumori 1987;73:29-31.. PubMed
- Thapliyal R, Deshpande SS, Maru GB. Mechanism(s) of turmeric-mediated protective effects against benzo(a)pyrene-derived DNA adducts. Cancer Lett 2002;175:79-88. PubMed
- Lee SW, Nah SS, Byon JS, et al. Transient complete atrioventricular block associated with curcumin intake. Int J Cardiol 2011;150:e50-2. PubMed
- Kuptniratsaikul V, Thanakhumtorn S, Chinswangwatanakul P, et al. Efficacy and safety of Curcuma domestica extracts in patients with knee osteoarthritis. J Altern Complement Med 2009;15:891-7.
- Carroll RE, Benya RV, Turgeon DK, et al. Phase IIa clinical trial of curcumin for the prevention of colorectal neoplasia. Cancer Prev Res (Phila) 2011;4:354-64. PubMed
- Junyaprasert, V. B., Soonthornchareonnon, N., Thongpraditchote, S., Murakami, T., and Takano, M. Inhibitory effect of Thai plant extracts on P-glycoprotein mediated efflux. Phytother.Res 2006;20(1):79-81. PubMed
- Ampasavate, C., Sotanaphun, U., Phattanawasin, P., and Piyapolrungroj, N. Effects of Curcuma spp. on P-glycoprotein function. Phytomedicine. 2010;17(7):506-512. PubMed
- Hou, X. L., Takahashi, K., Tanaka, K., Tougou, K., Qiu, F., Komatsu, K., Takahashi, K., and Azuma, J. Curcuma drugs and curcumin regulate the expression and function of P-gp in Caco-2 cells in completely opposite ways. Int.J Pharm 6-24-2008;358(1-2):224-2 PubMed
- Choi, B. H., Kim, C. G., Lim, Y., Shin, S. Y., and Lee, Y. H. Curcumin down-regulates the multidrug-resistance mdr1b gene by inhibiting the PI3K/Akt/NF kappa B pathway. Cancer Lett. 1-18-2008;259(1):111-118.
- Zhang, W., Tan, T. M., and Lim, L. Y. Impact of curcumin-induced changes in P-glycoprotein and CYP3A expression on the pharmacokinetics of peroral celiprolol and midazolam in rats. Drug Metab Dispos. 2007;35(1):110-115. PubMed
- Limtrakul, P., Chearwae, W., Shukla, S., Phisalphong, C., and Ambudkar, S. V. Modulation of function of three ABC drug transporters, P-glycoprotein (ABCB1), mitoxantrone resistance protein (ABCG2) and multidrug resistance protein 1 (ABCC1) by tetrahydrocu
- Holland, M. L., Panetta, J. A., Hoskins, J. M., Bebawy, M., Roufogalis, B. D., Allen, J. D., and Arnold, J. C. The effects of cannabinoids on P-glycoprotein transport and expression in multidrug resistant cells. Biochem.Pharmacol 4-14-2006;71(8):1146-1154 PubMed
- Tang, X. Q., Bi, H., Feng, J. Q., and Cao, J. G. Effect of curcumin on multidrug resistance in resistant human gastric carcinoma cell line SGC7901/VCR. Acta Pharmacol Sin. 2005;26(8):1009-1016. PubMed
- Nabekura, T., Kamiyama, S., and Kitagawa, S. Effects of dietary chemopreventive phytochemicals on P-glycoprotein function. Biochem.Biophys.Res Commun. 2-18-2005;327(3):866-870. PubMed
- Romiti, N., Tongiani, R., Cervelli, F., and Chieli, E. Effects of curcumin on P-glycoprotein in primary cultures of rat hepatocytes. Life Sci. 1998;62(25):2349-2358. PubMed
- Yue, G. G., Cheng, S. W., Yu, H., Xu, Z. S., Lee, J. K., Hon, P. M., Lee, M. Y., Kennelly, E. J., Deng, G., Yeung, S. K., Cassileth, B. R., Fung, K. P., Leung, P. C., and Lau, C. B. The role of turmerones on curcumin transportation and P-glycoprotein acti
- Shenouda, N. S., Zhou, C., Browning, J. D., Ansell, P. J., Sakla, M. S., Lubahn, D. B., and MacDonald, R. S. Phytoestrogens in common herbs regulate prostate cancer cell growth in vitro. Nutr.Cancer 2004;49(2):200-208. PubMed
- Appiah-Opong, R., Commandeur, J. N., Vugt-Lussenburg, B., and Vermeulen, N. P. Inhibition of human recombinant cytochrome P450s by curcumin and curcumin decomposition products. Toxicology 6-3-2007;235(1-2):83-91. PubMed
- Hou, X. L., Takahashi, K., Kinoshita, N., Qiu, F., Tanaka, K., Komatsu, K., Takahashi, K., and Azuma, J. Possible inhibitory mechanism of Curcuma drugs on CYP3A4 in 1alpha,25 dihydroxyvitamin D3 treated Caco-2 cells. Int.J Pharm 6-7-2007;337(1-2):169-177.
- Valentine, S. P., Le Nedelec, M. J., Menzies, A. R., Scandlyn, M. J., Goodin, M. G., and Rosengren, R. J. Curcumin modulates drug metabolizing enzymes in the female Swiss Webster mouse. Life Sci. 4-11-2006;78(20):2391-2398. PubMed
- Price, R. J., Scott, M. P., Giddings, A. M., Walters, D. G., Stierum, R. H., Meredith, C., and Lake, B. G. Effect of butylated hydroxytoluene, curcumin, propyl gallate and thiabendazole on cytochrome P450 forms in cultured human hepatocytes. Xenobiotica 2 PubMed
- Ganta, S., Devalapally, H., and Amiji, M. Curcumin enhances oral bioavailability and anti-tumor therapeutic efficacy of paclitaxel upon administration in nanoemulsion formulation. J Pharm Sci 2010;99(11):4630-4641. PubMed
- Lamb, S. R. and Wilkinson, S. M. Contact allergy to tetrahydrocurcumin. Contact Dermatitis 2003;48(4):227. PubMed
- Joshi, J., Ghaisas, S., Vaidya, A., Vaidya, R., Kamat, D. V., Bhagwat, A. N., and Bhide, S. Early human safety study of turmeric oil (Curcuma longa oil) administered orally in healthy volunteers. J Assoc.Physicians India 2003;51:1055-1060.
- Mahesh, T., Balasubashini, M. S., and Menon, V. P. Effect of photo-irradiated curcumin treatment against oxidative stress in streptozotocin-induced diabetic rats. J Med.Food 2005;8(2):251-255. PubMed
- Thompson, D. A. and Tan, B. B. Tetrahydracurcumin-related allergic contact dermatitis. Contact Dermatitis 2006;55(4):254-255. PubMed
- Patumraj, S., Wongeakin, N., Sridulyakul, P., Jariyapongskul, A., Futrakul, N., and Bunnag, S. Combined effects of curcumin and vitamin C to protect endothelial dysfunction in the iris tissue of STZ-induced diabetic rats. Clin Hemorheol.Microcirc. 2006;3
- Liddle, M., Hull, C., Liu, C., and Powell, D. Contact urticaria from curcumin. Dermatitis 2006;17(4):196-197. PubMed
- Juan, H., Terhaag, B., Cong, Z., Bi-Kui, Z., Rong-Hua, Z., Feng, W., Fen-Li, S., Juan, S., Jing, T., and Wen-Xing, P. Unexpected effect of concomitantly administered curcumin on the pharmacokinetics of talinolol in healthy Chinese volunteers. Eur.J Clin PubMed
- Murugan, P. and Pari, L. Influence of tetrahydrocurcumin on erythrocyte membrane bound enzymes and antioxidant status in experimental type 2 diabetic rats. J Ethnopharmacol. 9-25-2007;113(3):479-486. PubMed
- Seo, K. I., Choi, M. S., Jung, U. J., Kim, H. J., Yeo, J., Jeon, S. M., and Lee, M. K. Effect of curcumin supplementation on blood glucose, plasma insulin, and glucose homeostasis related enzyme activities in diabetic db/db mice. Mol.Nutr.Food Res 2008;5
- Weisberg, S. P., Leibel, R., and Tortoriello, D. V. Dietary curcumin significantly improves obesity-associated inflammation and diabetes in mouse models of diabesity. Endocrinology 2008;149(7):3549-3558. PubMed
- Jain, S. K., Rains, J., Croad, J., Larson, B., and Jones, K. Curcumin supplementation lowers TNF-alpha, IL-6, IL-8, and MCP-1 secretion in high glucose-treated cultured monocytes and blood levels of TNF-alpha, IL-6, MCP-1, glucose, and glycosylated hemog
- Yu, Y., Hu, S. K., and Yan, H. [The study of insulin resistance and leptin resistance on the model of simplicity obesity rats by curcumin]. Zhonghua Yu Fang Yi.Xue.Za Zhi. 2008;42(11):818-822.
- Pavithra, B. H., Prakash, N., and Jayakumar, K. Modification of pharmacokinetics of norfloxacin following oral administration of curcumin in rabbits. J Vet.Sci. 2009;10(4):293-297. PubMed
- Yan, Y. D., Kim, D. H., Sung, J. H., Yong, C. S., and Choi, H. G. Enhanced oral bioavailability of docetaxel in rats by four consecutive days of pre-treatment with curcumin. Int J Pharm 10-31-2010;399(1-2):116-120. PubMed
- Epelbaum, R., Schaffer, M., Vizel, B., Badmaev, V., and Bar-Sela, G. Curcumin and gemcitabine in patients with advanced pancreatic cancer. Nutr Cancer 2010;62(8):1137-1141. PubMed
- Madkor, H. R., Mansour, S. W., and Ramadan, G. Modulatory effects of garlic, ginger, turmeric and their mixture on hyperglycaemia, dyslipidaemia and oxidative stress in streptozotocin-nicotinamide diabetic rats. Br J Nutr 2011;105(8):1210-1217. PubMed
- Pungcharoenkul, K. and Thongnopnua, P. Effect of different curcuminoid supplement dosages on total in vivo antioxidant capacity and cholesterol levels of healthy human subjects. Phytother Res 2011;25(11):1721-1726.
- Kusuhara, H., Furuie, H., Inano, A., Sunagawa, A., Yamada, S., Wu, C., Fukizawa, S., Morimoto, N., Ieiri, I., Morishita, M., Sumita, K., Mayahara, H., Fujita, T., Maeda, K., and Sugiyama, Y. Pharmacokinetic interaction study of sulphasalazine in healthy
- Mohammadi, A., Sahebkar, A., Iranshahi, M., Amini, M., Khojasteh, R., Ghayour-Mobarhan, M., and Ferns, G. A. Effects of supplementation with curcuminoids on dyslipidemia in obese patients: a randomized crossover trial. Phytother Res 2013;27(3):374-379. PubMed
- Chuengsamarn, S., Rattanamongkolgul, S., Luechapudiporn, R., Phisalaphong, C., and Jirawatnotai, S. Curcumin extract for prevention of type 2 diabetes. Diabetes Care 2012;35(11):2121-2127. PubMed
- Goh, C. L. and Ng, S. K. Allergic contact dermatitis to Curcuma longa (turmeric). Contact Dermatitis 1987;17(3):186. PubMed
- Srivastava, R., Puri, V., Srimal, R. C., and Dhawan, B. N. Effect of curcumin on platelet aggregation and vascular prostacyclin synthesis. Arzneimittelforschung. 1986;36(4):715-717.
- Srinivasan, M. Effect of curcumin on blood sugar as seen in a diabetic subject. Indian J Med Sci 1972;26(4):269-270.
- Srivastava, K. C., Bordia, A., and Verma, S. K. Curcumin, a major component of food spice turmeric (Curcuma longa) inhibits aggregation and alters eicosanoid metabolism in human blood platelets. Prostaglandins Leukot.Essent.Fatty Acids 1995;52(4):223-227 PubMed
- Oetari, S., Sudibyo, M., Commandeur, J. N., Samhoedi, R., and Vermeulen, N. P. Effects of curcumin on cytochrome P450 and glutathione S-transferase activities in rat liver. Biochem Pharmacol 1-12-1996;51(1):39-45. PubMed
- Kiec-Swierczynska, M. and Krecisz, B. Occupational allergic contact dermatitis due to curcumin food colour in a pasta factory worker. Contact Dermatitis 1998;39(1):30-31. PubMed
- Van Dau N, Ngoc Ham N, Huy Khac D, and et al. The effects of a traditional drug, tumeric (Curcuma longa), and placebo on the healing of duodenal ulcer. Phytomed 1998;5(1):29-34.
- Daveluy A, Géniaux H, Thibaud L, Mallaret M, Miremont-Salamé G, Haramburu F. Probable interaction between an oral vitamin K antagonist and turmeric (Curcuma longa). Therapie. 2014 Nov-Dec;69(6):519-20. PubMed
- Kuptniratsaikul V, Dajpratham P, Taechaarpornkul W, Buntragulpoontawee M, Lukkanapichonchut P, Chootip C, Saengsuwan J, Tantayakom K, Laongpech S. Efficacy and safety of Curcuma domestica extracts compared with ibuprofen in patients with knee osteoarthrit
- Madhu K, Chanda K, Saji MJ. Safety and efficacy of Curcuma longa extract in the treatment of painful knee osteoarthritis: a randomized placebo-controlled trial. Inflammopharmacology 2013;21(2):129-36. PubMed
- Mali AM, Behal R, Gilda SS. Comparative evaluation of 0.1% turmeric mouthwash with 0.2% chlorhexidine gluconate in prevention of plaque and gingivitis: A clinical and microbiological study. J Indian Soc Periodontol 2012;16(3):386-91. PubMed
- Sanmukhani J, Satodia V, Trivedi J, Patel T, Tiwari D, Panchal B, Goel A, Tripathi CB. Efficacy and safety of curcumin in major depressive disorder: a randomized controlled trial. Phytother Res 2014;28(4):579-85. PubMed
- Nayeri A, Wu S, Adams E, et al. Acute Calcineurin Inhibitor Nephrotoxicity Secondary to Turmeric Intake: A Case Report. Transplant Proc. 2017;49(1):198-200. PubMed
- Mitchell TM. Correspondence re: Somasundaram et al., Dietary curcumin inhibits chemotherapy-induced apoptosis in models of human breast cancer. Cancer Res. 2003;63(16):5165-6; author reply 5166-7.
- Somasundaram S, Edmund NA, Moore DT, Small GW, Shi YY, Orlowski RZ. Dietary curcumin inhibits chemotherapy-induced apoptosis in models of human breast cancer. Cancer Res. 2002;62(13):3868-75.
- Haroyan A, Mukuchyan V, Mkrtchyan N, et al. Efficacy and safety of curcumin and its combination with boswellic acid in osteoarthritis: a comparative, randomized, double-blind, placebo-controlled study. BMC Complement Altern Med. 2018;18(1):7. PubMed
- Al-Karawi D, Al Mamoori DA, Tayyar Y. The role of curcumin administration in patients with major depressive disorder: Mini meta-analysis of clinical trials. Phytother Res. 2016;30(2):175-83. PubMed
- Neerati P, Devde R, Gangi AK. Evaluation of the effect of curcumin capsules on glyburide therapy in patients with type-2 diabetes mellitus. Phytother Res. 2014;28(12):1796-800. PubMed
- Simental-Mendía LE, Pirro M, Gotto AM Jr, et al. Lipid-modifying activity of curcuminoids: A systematic review and meta-analysis of randomized controlled trials. Crit Rev Food Sci Nutr. 2017:1-10. PubMed
- Fung FY, Wong WH, Ang SK, et al. A randomized, double-blind, placebo- controlled study on the anti-haemostatic effects of Curcuma longa, Angelica sinensis and Panax ginseng. Phytomedicine. 2017;32:88-96. PubMed
- Small GW, Siddarth P, Li Z, et al. Memory and brain amyloid and tau effects of a bioavailable form of curcumin in non-demented adults: A double-blind, placebo-controlled 18-month trial. Am J Geriatr Psychiatry. 2018;26(3):266-277.
- Cruz-Correa M, Hylind LM, Marrero JH, et al. Efficacy and safety of curcumin in treatment of intestinal adenomas in patients with familial adenomatous polyposis. Gastroenterology. 2018 May 23. Pii:S0016-5085(18)34564-5. [Epub ahead of print] PubMed
- Rahmani S, Asgary S, Askari G, et al. Treatment of non-alcoholic fatty liver disease with curcumin: a randomized placebo-controlled trial. Phytother Res. 2016 Sep;30(9):1540-8. PubMed
- Lopez-Villafuerte L, CLores KH. Contact dermatitis caused by turmeric in a massage oil. Contact Dermatitis. 2016 Jul;75(1):52-3. PubMed
- Lukefahr AL, McEvoy S, Alfafara C, Funk JL. Drug-induced autoimmune hepatitis associated with turmeric dietary supplement use. BMJ Case Rep. 2018. pii: bcr-2018-224611. PubMed
- Medsafe Safety Communication- Turmeric/Curcumin Interaction with Warfarin. April 30, 2018. Accessed at: https://medsafe.govt.nz/safety/EWS/2018/Turmeric.asp.
- Imam Z, Khasawneh M, Jomaa D, Iftikhar H, Sayedahmad Z. Drug induced liver injury attributed to a curcumin supplement. Case Rep Gastrointest Med 2019 Oct 20;2019:6029403. doi: 10.1155/2019/6029403. PubMed
- Chand S, Hair C, Beswick L. A rare case of turmeric-induced hepatotoxicity. Intern Med J. 2020;50(2):258-259. PubMed
- Jiang N, Zhang M, Meng X, Sun B. Effects of Curcumin on the Pharmacokinetics of Amlodipine in Rats and Its Potential Mechanism. Pharm Biol. 2020;58(1):465-468. PubMed
- Lee BS, Bhatia T, Chaya CT, Wen R, Taira MT, Lim BS. Autoimmune Hepatitis Associated With Turmeric Consumption. ACG Case Rep J. 2020;7(3):e00320. PubMed
- Lombardi N, Crescioli G, Maggini V, et al. Acute liver injury following turmeric use in Tuscany: an analysis of the Italian Phytovigilance database and systematic review of case reports. Br J Clin Pharmacol. 2020. PubMed
- Suhail FK, Masood U, Sharma A, John S, Dhamoon A. Turmeric supplement induced hepatotoxicity: a rare complication of a poorly regulated substance. Clin Toxicol (Phila). 2020;58(3):216-217. PubMed
- Nakagawa Y, Mukai S, Yamada S, et al. The efficacy and safety of highly-bioavailable curcumin for treating knee osteoarthritis: a 6-month open-labeled prospective study. Clin Med Insights Arthritis Musculoskelet Disord. 2020;13:1179544120948471. PubMed
- Shafabakhsh R, Asemi Z, Reiner Z, Soleimani A, Aghadavod E, Bahmani F. The effects of nano-curcumin on metabolic status in patients with diabetes on hemodialysis, a randomized, double blind, placebo-controlled trial. Iran J Kidney Dis. 2020;14(4):290-9.
- Allegri P, Rosa R, Masala A, et al. Clinical effectiveness of a new oral curcumin formulation in acute non-infectious uveitic macular edema: a 12-month observational study. Eur Rev Med Pharmacol Sci 2022;26(1):46-53.
- Tsai IC, Hsu CW, Chang CH, Tseng PT, Chang KV. The effect of curcumin differs on individual cognitive domains across different patient populations: A systematic review and meta-analysis. Pharmaceuticals (Basel) 2021;14(12):1235. PubMed
- Alam MA, Bin Jardan YA, Raish M, Al-Mohizea AM, Ahad A, Al-Jenoobi FI. Herb-drug interaction: Pharmacokinetics and pharmacodynamics of anti-hypertensive drug amlodipine besylate in presence of lepidium sativum and curcuma longa. Xenobiotica 2022;1-9.
- Sohal A, Alhankawi D, Sandhu S, Chintanaboina J. Turmeric-induced hepatotoxicity: Report of 2 cases. Int Med Case Rep J 2021;14:849-852. PubMed
- Hussaarts KGAM, Hurkmans DP, Oomen-de Hoop E, et al. Impact of curcumin (with or without piperine) on the pharmacokinetics of tamoxifen. Cancers (Basel). 2019;11(3):403. PubMed
- Kalluru H, Mallayasamy SR, Kondaveeti SS, Chandrasekhar V, Kalachaveedu M. Effect of turmeric supplementation on the pharmacokinetics of paclitaxel in breast cancer patients: A study with population pharmacokinetics approach. Phytother Res 2022;36(4):1761 PubMed
- 109288 Halegoua-DeMarzio D, Navarro V, Ahmad J, et al. Liver injury associated with turmeric-A growing problem: Ten cases from the drug-induced liver injury network [DILIN]. Am J Med. 2022:S0002-9343(22)00740-9. PubMed
- Arzallus T, Izagirre A, Castiella A, Torrente S, Garmendia M, Zapata EM. Drug induced autoimmune hepatitis after turmeric intake. Gastroenterol Hepatol 2023. PubMed
- Gilad O, Rosner G, Ivancovsky-Wajcman D, et al. Efficacy of wholistic turmeric supplement on adenomatous polyps in patients with familial adenomatous polyposis-A randomized, double-blinded, placebo-controlled study. Genes (Basel) 2022;13(12):2182. PubMed
- Ahad A, Raish M, Abdelrahman IA, et al. Changes in pharmacokinetics and pharmacodynamics of losartan in experimental diseased rats treated with Curcuma longa and Lepidium sativum. Pharmaceuticals (Basel) 2022;16(1):33. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
- Kou H, Huang L, Jin M, He Q, Zhang R, Ma J. Effect of curcumin on rheumatoid arthritis: a systematic review and meta-analysis. Front Immunol 2023;14:1121655. PubMed
- Qiu L, Gao C, Wang H, et al. Effects of dietary polyphenol curcumin supplementation on metabolic, inflammatory, and oxidative stress indices in patients with metabolic syndrome: a systematic review and meta-analysis of randomized controlled trials. Front PubMed
- Sato T, Yagi A, Yamauchi M, et al. The use of an antioxidant enables accurate evaluation of the interaction of curcumin on organic anion-transporting polypeptides 4C1 by preventing auto-oxidation. Int J Mol Sci 2024;25(2):991. PubMed
- Washington O, Robinson E, Simh D, et al. Oxalate nephropathy and chronic turmeric supplementation: a case report. J Bras Nefrol 2024;46(1):99-106. PubMed
- Munshi R, Karande-Patil S, Kumbhar D, Deshmukh A, Hingorani L. A randomized, controlled, comparative, proof-of-concept study to evaluate the efficacy and safety of Nisha-Amalaki capsules in prediabetic patients for preventing progression to diabetes. J Ay PubMed
- Sharifi Razavi A, Mohajerani F, Niksolat F, Karimi N. Efficacy of topical curcumin on mild to moderate carpal tunnel syndrome: a randomized double-blind, placebo-controlled clinical trial. Pain Med 2024;25(5):327-333. PubMed
- Yaikwawong M, Jansarikit L, Jirawatnotai S, Chuengsamarn S. Curcumin Reduces Depression in Obese Patients with Type 2 Diabetes: A Randomized Controlled Trial. Nutrients 2024;16(15):2414. PubMed
- Tehrani SD, Hosseini A, Shahzamani M, et al. Evaluation of the effectiveness of curcumin and piperine co-supplementation on inflammatory factors, cardiac biomarkers, atrial fibrillation, and clinical outcomes after coronary artery bypass graft surgery. Cl PubMed
- Yaikwawong M, Jansarikit L, Jirawatnotai S, Chuengsamarn S. The Effect of Curcumin on Reducing Atherogenic Risks in Obese Patients with Type 2 Diabetes: A Randomized Controlled Trial. Nutrients 2024;16(15):2441. PubMed
- Dibaei M, Hosseini A, Lavasani H, Kiani-Dehkordi B, Rouini M. Assessment of metabolic interaction between curcumin and tramadol using the isolated perfused rat liver. Heliyon 2024;10(15):e35070. PubMed
Devil's Claw 18 references
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
- Shaw D, Leon C, Kolev S, Murray V. Traditional remedies and food supplements: a 5-year toxicological study (1991-1995). Drug Saf 1997;17:342-56.
- Chantre P, Cappelaere A, Leblan D, et al. Efficacy and tolerance or Harpagophytum procumbens versus diacerhein in treatment of osteoarthritis. Phytomedicine 2000;7:177-83.
- Chrubasik S, Thanner J, Kunzel O, et al. Comparison of outcome measures during treatment with the proprietary Harpagophytum extract doloteffin in patients with pain in the lower back, knee or hip. Phytomedicine 2002;9:181-94. PubMed
- Circosta C, Occhiuto F, Ragusa S, et al. A drug used in traditional medicine: Harpagophytum procumbens DC. II. Cardiovascular activity. J Ethnopharmacol 1984;11:259-74. PubMed
- Grahame R, Robinson BV. Devils's claw (Harpagophytum procumbens): pharmacological and clinical studies. Ann Rheum Dis 1981;40:632. PubMed
- Unger M, Frank A. Simultaneous determination of the inhibitory potency of herbal extracts on the activity of six major cytochrome P450 enzymes using liquid chromatography/mass spectrometry and automated online extraction. Rapid Commun Mass Spectrom 2004;1 PubMed
- Wegener T, Lupke NP. Treatment of patients with arthrosis of hip or knee with an aqueous extract of devil's claw (Harpagophytum procumbens DC). Phytother Res 2003;17:1165-72.
- Chrubasik S, Kunzel O, Thanner J, et al. A 1-year follow-up after a pilot study with Doloteffin for low back pain. Phytomedicine 2005;12:1-9. PubMed
- Romiti N, Tramonti G, Corti A, Chieli E. Effects of Devil's Claw (Harpagophytum procumbens) on the multidrug transporter ABCB1/P-glycoprotein. Phytomedicine 2009;16:1095-100. PubMed
- Chrubasik, S., Junck, H., Breitschwerdt, H., Conradt, C., and Zappe, H. Effectiveness of Harpagophytum extract WS 1531 in the treatment of exacerbation of low back pain: a randomized, placebo-controlled, double- blind study. Eur.J Anaesthesiol. 1999;16(2 DOI
- Laudahn, D. and Walper, A. Efficacy and tolerance of Harpagophytum extract LI 174 in patients with chronic non-radicular back pain. Phytother.Res. 2001;15(7):621-624.
- Belaiche P. Etude clinique de 630 cas d'artrose traites par le nebulisat aqueux d'Harpagophytum procumbens (Radix). Phytotherapy 1982;1:22-28.
- Chrubasik S, Model A, Black A, and et al. A randomized double-blind pilot study comparing Doloteffin® and Vioxx® in the treatment of low back pain. Rheumatology 2003;42:141-148.
- Cuspidi C, Sala C, Tadic M, et al. Systemic hypertension induced by Harpagophytum procumbens (devil's claw): a case report. J Clin Hypertens (Greenwich) 2015;17(11):908-10.
- Mahomed IM, Ojewole JAO. Oxytocin-like effect of Harpagophytum procumbens [Pedaliacae] secondary root aqueous extract on rat isolated uterus. Afr J Trad CAM 2006;3(1):82-89.
- Carvalho RR, Donadel CD, Cortez AF, Valviesse VR, Vianna PF, Correa BB. J Bras Nefrol. 2017 Mar;39(1):79-81.
- Anon. Devil's claw root: ulcers and gastrointestinal bleeding. Prescrire Int 2013;22(144):296.
Boswellia Serrata 16 references
- Gupta I, Gupta V, Parihar A, et al. Effects of Boswellia serrata gum resin in patients with bronchial asthma: results of a double-blind, placebo-controlled, 6-week clinical study. Eur J Med Res 1998;3:511-4.
- Electronic Code of Federal Regulations. Title 21. Part 182 -- Substances Generally Recognized As Safe. Available at: https://www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfcfr/CFRSearch.cfm?CFRPart=182
- Kimmatkar N, Thawani V, Hingorani L, et al. Efficacy and tolerability of Boswellia serrata extract in treatment of osteoarthritis of knee--a randomized double blind placebo controlled trial. Phytomedicine 2003;10:3-7. PubMed
- Liu JJ, Nilsson A, Oredsson S, et al. Boswellic acids trigger apoptosis via a pathway dependent on caspase-8 activation but independent on Fas/Fas ligand interaction in colon cancer HT-29 cells. Carcinogenesis 2002;23:2087-93. PubMed
- Wildfeuer A, Neu IS, Safayhi H, et al. Effects of boswellic acids extracted from a herbal medicine on the biosynthesis of leukotrienes and the course of experimental autoimmune encephalomyelitis. Arzneimittelforschung 1998;48:668-74.
- Gupta I, Parihar A, Malhotra P, et al. Effects of gum resin of Boswellia serrata in patients with chronic colitis. Planta Med 2001;67:391-5. PubMed
- Sengupta K, Alluri KV, Satish AR, et al. A double blind, randomized, placebo controlled study of the efficacy and safety of 5-Loxin. Arthritis Res Ther 2008;10:R85.
- Sengupta K, Krishnaraju AV, Vishal AA, et al. Comparative efficacy and tolerability of 5-Loxin and Aflapin against osteoarthritis of the knee: a double blind, randomized, placebo controlled clinical study. Int J Med Sci 2010;7:366-77.
- Ernst E. Frankincense: systematic review. BMJ 2008;337:a2813. PubMed
- Kirste S, Treier M, Wehrle SJ, et al. Boswellia serratea extract acts on cerebral edema in patients irradiated for brain tumors: a prospective, randomized, placebo-controlled, double-blind pilot trial. Cancer 2011;117:3788-95.
- Frank A, Unger M. Analysis of frankincense from various Boswellia species with inhibitory activity on human drug metabolising cytochrome P450 enzymes using liquid chromatography mass spectrometry after automated on-line extraction. J Chromatogr A 2006;111 PubMed
- Altmann A, Poeckel D, Fischer L, et al. Coupling of boswellic acid-incuded Ca2+ mobilisation and MAPK activation to lipid metabolism and peroxide formation in human leucocytes. Br J Pharmacol 2004;141:223-32.
- El Fortia, M., Badi, H., Elalem, Kh, Kadiki, O., and Topov, Y. Olibanum bezoar: complication of a traditional popular medicine. East Mediterr.Health J 2006;12(6):927-929.
- Meshkat S, Mahmoodi Baram S, Rajaei S, et al. Boswellia serrata extract shows cognitive benefits in a double-blind, randomized, placebo-controlled pilot clinical trial in individuals who suffered traumatic brain injury. Brain Inj 2022;36(4):553-559. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Valente IVB, Garcia D, Abbott A, et al. The anti-proliferative effects of a frankincense extract in a window of opportunity phase ia clinical trial for patients with breast cancer. Breast Cancer Res Treat 2024;204(3):521-530. PubMed
Yucca 3 references
- <p><span>Kanerva, L., Estlander, T., Petman, L., Makinen-Kiljunen, S. Occupational allergic contact urticaria to yucca (Yucca aloifolia), weeping fig (Ficus benjamina), and spathe flower (Spathiphyllum wallisii). Allergy. 2001;56(10): 1008-11.</span></p>
- Poljacki, M., Paravina, M., Jovanovic, M., Subotic, M., and Duran, V. [Contact allergic dermatitis caused by plants]. Med Pregl. 1993;46(9-10):371-375.
- Mahillon, V., Saussez, S., and Michel, O. High incidence of sensitization to ornamental plants in allergic rhinitis. Allergy 2006;61(9):1138-1140. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC