
LeptiCell Ingredients & Drug Interactions
by PhytAge Labs
What is this page for?
First and foremost: checking LeptiCell against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
LeptiCell is a dietary supplement by PhytAge Labs with 23 active ingredients. Its ingredients are commonly taken for morning sickness in pregnancy, premenstrual syndrome (pms), preventing or treating b6 deficiency.Based on those ingredients, 1,591 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Ashwagandha, Bioperine, Ginger. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against LeptiCell by PhytAge Labs
Ask about any prescription or over-the-counter medication and we check it for interactions with LeptiCell by PhytAge Labs — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of LeptiCell by PhytAge Labs
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
LeptiCell contains 23 active ingredients spanning vitamins, amino acids, herbal extracts, and botanicals. The vitamins include B6, B12, B1, B3, pantothenic acid, and vitamin A.
The amino acids are L-arginine and L-tyrosine. The herbal and botanical actives include bioperine (black pepper), maca, tribulus terrestris, asparagus, ginger, damiana, dong quai (angelica sinensis), mucuna pruriens seed extract, muira puama, sarsaparilla, ashwagandha, catuaba, sea buckthorn fruit oil, horny goat weed, and zinc.
The product also contains inactive ingredients—hypromellose, magnesium stearate, silica, and rice flour—which are fillers and capsule materials.
Does it work?
Moderate evidence
The evidence for effectiveness varies widely among LeptiCell's ingredients and depends on what you're taking it for. Vitamin B6 is effective for sideroblastic anemia and vitamin B6 deficiency, and possibly effective for pregnancy-induced nausea.
Vitamin B12 is effective for B12 deficiency. L-arginine, L-tyrosine, most of the herbal ingredients (maca, tribulus, damiana, muira puama, sarsaparilla, catuaba, horny goat weed), and several others have insufficient reliable evidence or possibly ineffective ratings for the conditions they're often marketed for.
Ashwagandha is possibly effective for insomnia, anxiety, and stress. Ginger is possibly effective for pregnancy-induced nausea and dysmenorrhea.
Zinc is possibly effective for acne and age-related macular degeneration. Because this is a multi-ingredient supplement and the product facts don't state a specific health claim, talk with your pharmacist about what you're hoping to achieve.
How safe is it?
Well-documented data
Several ingredients carry cautions about long-term or high-dose use. Vitamin B6 can cause nerve damage (sensory neuropathy) at very high doses or with prolonged use, though normal dietary amounts and standard supplement doses are safe.
L-arginine, L-tyrosine, tribulus, damiana, muira puama, and sarsaparilla all have limited human safety data and are generally advised only under medical supervision. Ashwagandha is generally well tolerated short-term but rare cases of liver injury have been reported.
Ginger is generally well tolerated at typical amounts. Zinc is safe below 40 mg daily but high doses can cause copper deficiency over time.
Dong quai can increase skin sensitivity to sunlight. Most common mild side effects across these ingredients include gastrointestinal upset, headache, and nausea.
Meds to double-check
Major interaction found
Before taking LeptiCell, double-check these medication types with your pharmacist: blood thinners like warfarin (major risk from dong quai), blood pressure medications including ACE inhibitors and ARBs (moderate risk from multiple ingredients), diabetes medications (moderate risk from several ingredients), antibiotics especially quinolones and tetracyclines (moderate risk from zinc), heart rhythm drugs, and any psychiatric or neurological medications. If you take levodopa for Parkinson's disease, do not take this product without medical clearance—it contains mucuna pruriens, which is a source of levodopa itself.
The bottom line
Scorecard at a glanceFully disclosed formula with some supporting evidence for its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
LeptiCell is a complex multi-ingredient supplement with significant interaction potential, especially if you take blood pressure medications, diabetes drugs, blood thinners, or antibiotics. Before starting this product, check each of your prescription and over-the-counter medications using the interaction tool on this page.
If you're pregnant, breastfeeding, or have liver or kidney disease, talk with your pharmacist or doctor first, as several ingredients carry cautions in these situations. Many of the herbal ingredients have limited safety data, so this is not a product to self-treat with long-term without professional guidance.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 22 of 23 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated May 21, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about LeptiCell, straight from the product label.
| Brand | PhytAge Labs |
|---|---|
| Net contents | 60 Capsule(s) |
| Market status | On market |
| Date entered into DSLD | May 21, 2025 |
| DSLD ID | 330111 |
| Product type | Botanical With Nutrients |
| Supplement form | Capsule |
| Dietary claims / uses | Nutrient, All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Women (not pregnant or lactating) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
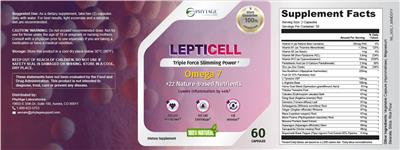
Supplement Facts
The label details for LeptiCell by PhytAge Labs, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Vitamin B6 | 3.8 mg | 224% |
| Vitamin B12 | 54 mcg | 2250% |
| L-Arginine | 100 mg | -- |
| L-Tyrosine | 100 mg | -- |
| Zinc | 26 mg | 236% |
| Vitamin B1 | 1.25 mg | 125% |
| Bioperine | 0.5 mg | -- |
| Vitamin B3 | 1 mg | 6% |
| Maca | 67 mg | -- |
| Tribulus terrestris | 67 mg | -- |
| Asparagus | 66 mg | -- |
| Ginger | 67 mg | -- |
| Damiana | 67 mg | -- |
| Angelica sinensis | 67 mg | -- |
| Vitamin A | 50 mcg RAE | 6% |
| Mucuna pruriens Seed Extract | 67 mg | -- |
| Muira Puama | 67 mg | -- |
| Sarsaparilla | 66 mg | -- |
| Pantothenic Acid | 2.5 mg | 50% |
| Ashwagandha | 67 mg | -- |
| Catuaba | 67 mg | -- |
| Sea Buckthorn Fruit Oil | 250 mg | -- |
| Horny Goat Weed | 67 mg | -- |
Other ingredients: Hypromellose, Magnesium Stearate, Silica, Rice Flour
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Suggested/Recommended/Usage/Directions
Suggested Use: As a dietary supplement, take two (2) capsules daily with water. For best results, light exercise and a sensible diet are recommended.
Precautions
Caution/Warning: Do not exceed recommended dose. Do not use if safety seal is damaged or missing.
Not for use for those under the age of 18 or pregnant or nursing mothers. Consult with a physician prior to use especially if you are taking a medication or have a medical condition.
Not for use for those under the age of 18 or pregnant or nursing mothers. Consult with a physician prior to use especially if you are taking a medication or have a medical condition. Keep out of reach of children.
Storage
Storage: Store this product in a cool dry place below 30 degrees C (86 degrees F). Store in a cool, dry place.
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure or prevent any disease.
Seals/Symbols
5 Stars Guarantee 100% Satisfaction
Formulation
Triple force slimming power Lowers inflammation by 44% Fat cell breakdown Fat cell shrinkage Fat release 100% Natural
Formula
Omega 7 +22 Nature-based nutrients
FDA Statement of Identity
Dietary Supplement
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
LeptiCell by PhytAge Labs label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in LeptiCell by PhytAge Labs
These are the 23 active ingredients this product is made of. Select any to open its full monograph.
Serving size2 Capsule(s) Dosage formCapsule Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Vitamin B6
Interacts with210 drugs
Vitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is b...
Vitamin B6 monograph & interactionsVitamin B12
Interacts with20 drugs
Vitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very h...
Vitamin B12 monograph & interactionsL-Arginine
Interacts with403 drugs
L-arginine is an amino acid that the body uses to make nitric oxide, a substance that helps blood vessels relax and widen. It is popularly used for bl...
L-Arginine monograph & interactionsL-Tyrosine
Interacts with21 drugs
L-tyrosine is an amino acid your body uses to make brain chemicals like dopamine and norepinephrine. Some studies suggest it may help mental performan...
L-Tyrosine monograph & interactionsZinc
Interacts with67 drugs
Zinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but suppleme...
Zinc monograph & interactionsVitamin B1
Bioperine
Interacts with1,019 drugs
Black pepper is a common kitchen spice that is generally safe in the amounts used in food. Its extract, piperine, is mostly added to supplements to he...
Bioperine monograph & interactionsVitamin B3
Interacts with727 drugs
Niacin (vitamin B3) is an essential nutrient your body needs for energy and metabolism, and deficiency is uncommon in most developed countries. Prescr...
Vitamin B3 monograph & interactionsMaca
No knowninteractions
Maca is a nutrient-rich Andean root often used for energy, libido, and menopause symptoms. Early studies suggest it may modestly help sexual desire an...
Maca monograph & interactionsTribulus terrestris
Interacts with259 drugs
Tribulus is a plant supplement most often marketed to boost libido, testosterone, and athletic performance, but the human evidence behind these claims...
Tribulus terrestris monograph & interactionsAsparagus
Interacts with76 drugs
Asparagus is a nutritious vegetable that is safe and healthy to eat as part of a normal diet. Most of its claimed medicinal benefits, such as use as a...
Asparagus monograph & interactionsGinger
Interacts with1,007 drugs
Ginger is a widely used culinary spice with a long history in traditional medicine, and it has the strongest evidence for helping with nausea and vomi...
Ginger monograph & interactionsDamiana
Interacts with86 drugs
Damiana is a traditional herb most famous as an aphrodisiac and mild mood-lifter, but solid human evidence for any of its uses is very limited. It is...
Damiana monograph & interactionsAngelica sinensis
Interacts with163 drugs
Dong Quai is a traditional Chinese herb often called "female ginseng" and is mostly used for menstrual and menopausal complaints. High-quality scienti...
Angelica sinensis monograph & interactionsVitamin A
Interacts with387 drugs
Vitamin A is an essential nutrient important for vision, skin, immune function, and growth. Most people get enough from a balanced diet, and supplemen...
Vitamin A monograph & interactionsMucuna pruriens Seed Extract
Interacts with193 drugs
Cowhage (Mucuna pruriens) is a tropical legume best known as a natural source of L-dopa, the compound the body turns into dopamine. It is most studied...
Mucuna pruriens Seed Extract monograph & interactionsMuira Puama
No knowninteractions
Muira puama is a Brazilian plant traditionally used as an aphrodisiac and general tonic, often nicknamed 'potency wood.' Human research is very limite...
Muira Puama monograph & interactionsSarsaparilla
Interacts with2 drugs
Sarsaparilla is a traditional root used in teas, tonics, and old-fashioned root beer flavoring. Modern evidence for its health claims is very limited...
Sarsaparilla monograph & interactionsPantothenic Acid
No knowninteractions
Pantothenic acid is vitamin B5, an essential nutrient your body uses to turn food into energy. True deficiency is very rare because it is found in nea...
Pantothenic Acid monograph & interactionsAshwagandha
Interacts with1,372 drugs
Ashwagandha is an Ayurvedic herb most often taken to help with stress, anxiety, and sleep, and some small studies suggest it may help, though the evid...
Ashwagandha monograph & interactionsCatuaba
No knowninteractions
Catuaba is a Brazilian herbal bark long used as a traditional aphrodisiac and energy tonic, but there is very little reliable human research to show i...
Catuaba monograph & interactionsSea Buckthorn Fruit Oil
Interacts with289 drugs
Sea buckthorn is a berry-bearing shrub rich in vitamins, carotenoids, and fatty acids that people use for skin, eye, digestive, and heart health. Earl...
Sea Buckthorn Fruit Oil monograph & interactionsHorny Goat Weed
Interacts with963 drugs
Horny goat weed (Epimedium) is a traditional Chinese herb most often marketed for low libido and erectile problems, but solid human evidence for these...
Horny Goat Weed monograph & interactionsOther (inactive) ingredients: Hypromellose, Magnesium Stearate, Silica, Rice Flour. These complete the product’s ingredient list but are not active constituents.
LeptiCell by PhytAge Labs Drug Interactions
HelloPharmacist Interaction Report
LeptiCell by PhytAge Labs contains 23 ingredients, many of which interact with medications.
The most serious interaction is with warfarin (a blood thinner), where dong quai—one of the product's herbal components—may increase bleeding risk significantly.
Read the full breakdown — every affected drug type, severity by severity
Several ingredients affect blood pressure control. Vitamin B6, L-arginine, tribulus, ashwagandha, sea buckthorn, and horny goat weed all interact with antihypertensive drugs (the medications used to lower blood pressure), and some—particularly L-arginine—also interact with ACE inhibitors and ARBs, which are among the most commonly prescribed blood pressure drugs.
L-arginine also raises concerns with potassium-sparing diuretics and potassium-related drug classes.
Multiple ingredients affect blood sugar management. Vitamin B6, L-arginine, tribulus, ginger, damiana, and ashwagandha all interact with diabetes medications, potentially increasing the risk of low blood sugar (hypoglycemia).
Additionally, zinc interacts with several antibiotics—quinolones, tetracyclines, cephalexin, and penicillamine—by reducing their absorption; patients should separate doses by at least 2–6 hours depending on the antibiotic. Black pepper (bioperine) increases blood levels of several drugs including phenytoin, rifampin, and theophylline.
Ginger interacts with blood thinners and certain heart drugs. Mucuna pruriens seed extract contains levodopa and poses major risks with MAOIs and methyldopa, and moderate risks with antipsychotics and tricyclic antidepressants.
Altogether, these interactions span 1,562 individual medications.
To check whether your specific medications are affected, use the interaction search tool below with each drug name.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against LeptiCell?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in LeptiCell interact with 1,591 drugs. Click any drug to see the details.
18 of the 23 ingredients in LeptiCell interact with drugs. Each result below shows which ingredient is responsible. Ashwagandha Bioperine Ginger Horny Goat Weed Vitamin B3 L-Arginine Vitamin A Sea Buckthorn Fruit Oil Tribulus terrestris Vitamin B6 Mucuna pruriens Seed Extract Angelica sinensis Damiana Asparagus Zinc L-Tyrosine Vitamin B12 Sarsaparilla
AcitretinSoriatane
How Acitretin interacts with LeptiCell — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Acitretin interactionAlitretinoinPanretin
How Alitretinoin interacts with LeptiCell — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Alitretinoin interactionAmphetamineAdensys XR-ODT, Adzenys ER, Dyanavel XR, Mydayis
How Amphetamine interacts with LeptiCell — through 2 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Amphetamine interactionBioperineCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Bioperine + Amphetamine interactionBenserazide, LevodopaMadopar, Prolopa
How Benserazide, Levodopa interacts with LeptiCell — through 3 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractLevodopa Major
Interaction Summary
Concomitant use can increase the risk of levodopa-related adverse effects.
Read the full Mucuna Pruriens Seed Extract + Benserazide, Levodopa interactionL-tyrosineLevodopa Moderate
Interaction Summary
Theoretically, tyrosine might decrease the effectiveness of levodopa.
Read the full L-tyrosine + Benserazide, Levodopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Benserazide, Levodopa interactionBexaroteneTargretin
How Bexarotene interacts with LeptiCell — through 5 ingredients. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Bexarotene interactionHorny Goat WeedCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP3A4 substrates.
Read the full Horny Goat Weed + Bexarotene interactionGingerCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger + Bexarotene interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Bexarotene interactionAshwagandhaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha + Bexarotene interactionCarbidopa, LevodopaDhivy, Rytary, Sinemet, Sinemet CR
How Carbidopa, Levodopa interacts with LeptiCell — through 3 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractLevodopa Major
Interaction Summary
Concomitant use can increase the risk of levodopa-related adverse effects.
Read the full Mucuna Pruriens Seed Extract + Carbidopa, Levodopa interactionL-tyrosineLevodopa Moderate
Interaction Summary
Theoretically, tyrosine might decrease the effectiveness of levodopa.
Read the full L-tyrosine + Carbidopa, Levodopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Carbidopa, Levodopa interactionCarbidopa, Levodopa, EntacaponeStalevo
How Carbidopa, Levodopa, Entacapone interacts with LeptiCell — through 3 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractLevodopa Major
Interaction Summary
Concomitant use can increase the risk of levodopa-related adverse effects.
Read the full Mucuna Pruriens Seed Extract + Carbidopa, Levodopa, Entacapone interactionL-tyrosineLevodopa Moderate
Interaction Summary
Theoretically, tyrosine might decrease the effectiveness of levodopa.
Read the full L-tyrosine + Carbidopa, Levodopa, Entacapone interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Carbidopa, Levodopa, Entacapone interactionChlorothiazide, MethyldopaAldochlor, Aldoclor 150, Aldoclor 250
How Chlorothiazide, Methyldopa interacts with LeptiCell — through 10 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMethyldopa (aldomet) Major
Interaction Summary
Theoretically, concomitant use of cowhage and methyldopa might increase the risk of hypotension.
Read the full Mucuna Pruriens Seed Extract + Chlorothiazide, Methyldopa interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Chlorothiazide, Methyldopa interactionAshwagandhaAntihypertensive Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with antihypertensive drugs might increase the risk of hypotension.
Read the full Ashwagandha + Chlorothiazide, Methyldopa interactionVitamin B3Antihypertensive Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
Read the full Vitamin B3 + Chlorothiazide, Methyldopa interactionL-arginineAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, concomitant use of L-arginine and antihypertensive drugs may increase the risk of hypotension.
Read the full L-arginine + Chlorothiazide, Methyldopa interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Chlorothiazide, Methyldopa interactionTribulus TerrestrisAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking tribulus with antihypertensive drugs might increase the risk of hypotension.
Read the full Tribulus Terrestris + Chlorothiazide, Methyldopa interactionAsparagusDiuretic Drugs Moderate
Interaction Summary
Theoretically, asparagus root might increase diuresis and electrolyte loss when used with diuretic drugs.
Read the full Asparagus + Chlorothiazide, Methyldopa interactionHorny Goat WeedAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, horny goat weed might increase the risk of hypotension.
Read the full Horny Goat Weed + Chlorothiazide, Methyldopa interactionSea Buckthorn Fruit OilAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking sea buckthorn with antihypertensive drugs might increase the risk of hypotension.
Read the full Sea Buckthorn Fruit Oil + Chlorothiazide, Methyldopa interactionHalobetasol Propionate,tazaroteneDuobrii
How Halobetasol Propionate,tazarotene interacts with LeptiCell — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Halobetasol Propionate,tazarotene interactionHydrochlorothiazide, MethyldopaAldoril 15, Aldoril 25, Aldoril D30, Methazide
How Hydrochlorothiazide, Methyldopa interacts with LeptiCell — through 10 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMethyldopa (aldomet) Major
Interaction Summary
Theoretically, concomitant use of cowhage and methyldopa might increase the risk of hypotension.
Read the full Mucuna Pruriens Seed Extract + Hydrochlorothiazide, Methyldopa interactionL-arginineAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, concomitant use of L-arginine and antihypertensive drugs may increase the risk of hypotension.
Read the full L-arginine + Hydrochlorothiazide, Methyldopa interactionVitamin B3Antihypertensive Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
Read the full Vitamin B3 + Hydrochlorothiazide, Methyldopa interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Hydrochlorothiazide, Methyldopa interactionAshwagandhaAntihypertensive Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with antihypertensive drugs might increase the risk of hypotension.
Read the full Ashwagandha + Hydrochlorothiazide, Methyldopa interactionTribulus TerrestrisAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking tribulus with antihypertensive drugs might increase the risk of hypotension.
Read the full Tribulus Terrestris + Hydrochlorothiazide, Methyldopa interactionAsparagusDiuretic Drugs Moderate
Interaction Summary
Theoretically, asparagus root might increase diuresis and electrolyte loss when used with diuretic drugs.
Read the full Asparagus + Hydrochlorothiazide, Methyldopa interactionHorny Goat WeedAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, horny goat weed might increase the risk of hypotension.
Read the full Horny Goat Weed + Hydrochlorothiazide, Methyldopa interactionSea Buckthorn Fruit OilAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking sea buckthorn with antihypertensive drugs might increase the risk of hypotension.
Read the full Sea Buckthorn Fruit Oil + Hydrochlorothiazide, Methyldopa interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Hydrochlorothiazide, Methyldopa interactionIsocarboxazidMarplan
How Isocarboxazid interacts with LeptiCell — through 2 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Isocarboxazid interactionAshwagandhaSerotonergic Drugs Minor
Interaction Summary
Some animal studies have reported that ashwagandha can enhance serotonergic transmission by altering certain serotonin (5-HT) receptors.
Read the full Ashwagandha + Isocarboxazid interactionIsotretinoinAbsorica, Accutane, Amnesteem, Claravis, Roaccutane, Sotret
How Isotretinoin interacts with LeptiCell — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Isotretinoin interactionLevodopaInbrija, Larodopa
How Levodopa interacts with LeptiCell — through 3 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractLevodopa Major
Interaction Summary
Concomitant use can increase the risk of levodopa-related adverse effects.
Read the full Mucuna Pruriens Seed Extract + Levodopa interactionL-tyrosineLevodopa Moderate
Interaction Summary
Theoretically, tyrosine might decrease the effectiveness of levodopa.
Read the full L-tyrosine + Levodopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Levodopa interactionLevodopa, CarbidopaDuodopa
How Levodopa, Carbidopa interacts with LeptiCell — through 3 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractLevodopa Major
Interaction Summary
Concomitant use can increase the risk of levodopa-related adverse effects.
Read the full Mucuna Pruriens Seed Extract + Levodopa, Carbidopa interactionL-tyrosineLevodopa Moderate
Interaction Summary
Theoretically, tyrosine might decrease the effectiveness of levodopa.
Read the full L-tyrosine + Levodopa, Carbidopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Levodopa, Carbidopa interactionMethyldopaAldomet, Methyldopa
How Methyldopa interacts with LeptiCell — through 9 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMethyldopa (aldomet) Major
Interaction Summary
Theoretically, concomitant use of cowhage and methyldopa might increase the risk of hypotension.
Read the full Mucuna Pruriens Seed Extract + Methyldopa interactionAshwagandhaAntihypertensive Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with antihypertensive drugs might increase the risk of hypotension.
Read the full Ashwagandha + Methyldopa interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Methyldopa interactionSea Buckthorn Fruit OilAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking sea buckthorn with antihypertensive drugs might increase the risk of hypotension.
Read the full Sea Buckthorn Fruit Oil + Methyldopa interactionL-arginineAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, concomitant use of L-arginine and antihypertensive drugs may increase the risk of hypotension.
Read the full L-arginine + Methyldopa interactionVitamin B3Antihypertensive Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
Read the full Vitamin B3 + Methyldopa interactionTribulus TerrestrisAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking tribulus with antihypertensive drugs might increase the risk of hypotension.
Read the full Tribulus Terrestris + Methyldopa interactionHorny Goat WeedAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, horny goat weed might increase the risk of hypotension.
Read the full Horny Goat Weed + Methyldopa interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Methyldopa interactionMoclobemideManerix, Moclobemide
How Moclobemide interacts with LeptiCell — through 1 ingredient. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Moclobemide interactionOzanimod HydrochlorideZeposia
How Ozanimod Hydrochloride interacts with LeptiCell — through 4 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Ozanimod Hydrochloride interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Ozanimod Hydrochloride interactionVitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + Ozanimod Hydrochloride interactionAshwagandhaHepatotoxic Drugs, Immunosuppressants Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Ozanimod Hydrochloride interactionPhenelzine SulfateNardil
How Phenelzine Sulfate interacts with LeptiCell — through 2 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Phenelzine Sulfate interactionAshwagandhaCns Depressants, Serotonergic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Ashwagandha + Phenelzine Sulfate interactionRasagilineAzilect
How Rasagiline interacts with LeptiCell — through 5 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Rasagiline interactionHorny Goat WeedCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP1A2 substrates.
Read the full Horny Goat Weed + Rasagiline interactionGingerCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Ginger + Rasagiline interactionAshwagandhaSerotonergic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Some animal studies have reported that ashwagandha can enhance serotonergic transmission by altering certain serotonin (5-HT) receptors.
Read the full Ashwagandha + Rasagiline interactionBioperineCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Rasagiline interactionSafinamide MesylateXadago
How Safinamide Mesylate interacts with LeptiCell — through 2 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Safinamide Mesylate interactionAshwagandhaSerotonergic Drugs Minor
Interaction Summary
Some animal studies have reported that ashwagandha can enhance serotonergic transmission by altering certain serotonin (5-HT) receptors.
Read the full Ashwagandha + Safinamide Mesylate interactionSelegilineCarbex, Eldepryl, Emsam, Zelapar
How Selegiline interacts with LeptiCell — through 2 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Selegiline interactionAshwagandhaSerotonergic Drugs Minor
Interaction Summary
Some animal studies have reported that ashwagandha can enhance serotonergic transmission by altering certain serotonin (5-HT) receptors.
Read the full Ashwagandha + Selegiline interactionTazaroteneArazlo, Avage, Fabior, Tazorotene, Zorac
How Tazarotene interacts with LeptiCell — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Tazarotene interactionTranylcypromineParnate
How Tranylcypromine interacts with LeptiCell — through 2 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Tranylcypromine interactionAshwagandhaSerotonergic Drugs Minor
Interaction Summary
Some animal studies have reported that ashwagandha can enhance serotonergic transmission by altering certain serotonin (5-HT) receptors.
Read the full Ashwagandha + Tranylcypromine interactionTretinoinAltreno, Renova, Retin-A, Vesanoid
How Tretinoin interacts with LeptiCell — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Tretinoin interactionTretinoin, Benzoyl PeroxideTwyneo
How Tretinoin, Benzoyl Peroxide interacts with LeptiCell — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Tretinoin, Benzoyl Peroxide interactionWarfarinWarfarin
How Warfarin interacts with LeptiCell — through 9 ingredients. Tap an ingredient for the detail:
Angelica SinensisAnticoagulant/antiplatelet Drugs, Warfarin (coumadin) Major
Interaction Summary
Theoretically, dong quai may increase the risk of bleeding when used with anticoagulant or antiplatelet drugs; however, research is conflicting.
Read the full Angelica Sinensis + Warfarin interactionHorny Goat WeedCytochrome P450 3a4 (cyp3a4) Substrates, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP3A4 substrates.
Read the full Horny Goat Weed + Warfarin interactionGingerAnticoagulant/antiplatelet Drugs, Warfarin (coumadin) +3 Moderate
Interaction Summary
Ginger may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Ginger + Warfarin interactionL-arginineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, concomitant use of L-arginine with anticoagulant and antiplatelet drugs might have additive effects and increase the risk of bleeding.
Read the full L-arginine + Warfarin interactionBioperineCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Warfarin interactionVitamin B3Warfarin (coumadin), Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
There is limited evidence that niacin may increase the anticoagulant effects of warfarin.
Read the full Vitamin B3 + Warfarin interactionSea Buckthorn Fruit OilAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, sea buckthorn may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Sea Buckthorn Fruit Oil + Warfarin interactionVitamin AWarfarin (coumadin) Moderate
Interaction Summary
Theoretically, high doses of vitamin A could increase the risk of bleeding with warfarin.
Read the full Vitamin A + Warfarin interactionAshwagandhaCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha + Warfarin interactionWarfarin SodiumCoumadin, Panwarfin, Sofarin
How Warfarin Sodium interacts with LeptiCell — through 9 ingredients. Tap an ingredient for the detail:
Angelica SinensisAnticoagulant/antiplatelet Drugs, Warfarin (coumadin) Major
Interaction Summary
Theoretically, dong quai may increase the risk of bleeding when used with anticoagulant or antiplatelet drugs; however, research is conflicting.
Read the full Angelica Sinensis + Warfarin Sodium interactionVitamin AWarfarin (coumadin) Moderate
Interaction Summary
Theoretically, high doses of vitamin A could increase the risk of bleeding with warfarin.
Read the full Vitamin A + Warfarin Sodium interactionVitamin B3Anticoagulant/antiplatelet Drugs, Warfarin (coumadin) Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Vitamin B3 + Warfarin Sodium interactionL-arginineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, concomitant use of L-arginine with anticoagulant and antiplatelet drugs might have additive effects and increase the risk of bleeding.
Read the full L-arginine + Warfarin Sodium interactionBioperineCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Warfarin Sodium interactionHorny Goat WeedCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP1A2 substrates.
Read the full Horny Goat Weed + Warfarin Sodium interactionGingerCytochrome P450 2c9 (cyp2c9) Substrates, Warfarin (coumadin) +3 Moderate
Interaction Summary
Theoretically, ginger might increase the levels of CYP2C9 substrates.
Read the full Ginger + Warfarin Sodium interactionSea Buckthorn Fruit OilAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, sea buckthorn may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Sea Buckthorn Fruit Oil + Warfarin Sodium interactionAshwagandhaCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha + Warfarin Sodium interactionEtretinateTegison
How Etretinate interacts with LeptiCell — through 1 ingredient. Tap an ingredient for the detail:
Vitamin ARetinoids Major
Interaction Summary
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Read the full Vitamin A + Etretinate interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with LeptiCell — through 3 ingredients. Tap an ingredient for the detail:
Vitamin AHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
Read the full Vitamin A + 6-mercaptopurine interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + 6-mercaptopurine interactionAshwagandhaHepatotoxic Drugs, Immunosuppressants Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with LeptiCell — through 4 ingredients. Tap an ingredient for the detail:
GingerCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger + Ado-trastuzumab Emtansine interactionHorny Goat WeedCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP3A4 substrates.
Read the full Horny Goat Weed + Ado-trastuzumab Emtansine interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Ado-trastuzumab Emtansine interactionAshwagandhaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha + Ado-trastuzumab Emtansine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in LeptiCell with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Ashwagandha
Antidiabetes Drugs
Theoretically, taking ashwagandha with antidiabetes drugs might increase the risk of hypoglycemia.
There is preliminary clinical evidence suggesting that ashwagandha might lower blood glucose levels. Theoretically, ashwagandha might have additive effects when used with antidiabetes drugs and increase the risk of hypoglycemia.
Antihypertensive Drugs
Theoretically, taking ashwagandha with antihypertensive drugs might increase the risk of hypotension.
Animal research suggests that ashwagandha might lower systolic and diastolic blood pressure. Theoretically, ashwagandha might have additive effects when used with antihypertensive drugs and increase the risk of hypotension.
Benzodiazepines
Theoretically, taking ashwagandha might increase the sedative effects of benzodiazepines.
There is preliminary evidence that ashwagandha might have an additive effect with diazepam (Valium) and clonazepam (Klonopin). This may also occur with other benzodiazepines.
Cns Depressants
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Ashwagandha seems to have sedative effects. Theoretically, this may potentiate the effects of barbiturates, other sedatives, and anxiolytics.
Hepatotoxic Drugs
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Ashwagandha has been linked to cases of acute hepatitis, liver failure, hepatic encephalopathy, autoimmune hepatitis, the need for liver transplantation, and death due to liver failure.
Immunosuppressants
Theoretically, taking ashwagandha might decrease the effects of immunosuppressants.
Ashwagandha has demonstrated immunostimulant effects in humans. Animal research has shown that ashwagandha can attenuate the immunosuppression caused by cyclophosphamide.
Thyroid Hormone
Ashwagandha might increase the effects and adverse effects of thyroid hormone.
Concomitant use of ashwagandha with thyroid hormones may cause additive therapeutic and adverse effects. Preliminary clinical research and animal studies suggest that ashwagandha boosts thyroid hormone synthesis and secretion. In one clinical study, ashwagandha increased triiodothyronine (T3) and thyroxine (T4) levels by 41.5% and 19.6%, respectively, and reduced serum TSH levels by 17.4% from baseline in adults with subclinical hypothyroidism.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
In vitro research shows that ashwagandha extract induces CYP1A2 enzymes.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
In vitro research shows that ashwagandha extract induces CYP3A4 enzymes.
Serotonergic Drugs
Some animal studies have reported that ashwagandha can enhance serotonergic transmission by altering certain serotonin (5-HT) receptors. However, there is no evidence to suggest that ashwagandha increases the risk of serotonin-related effects, and there have been no published case reports of serotonin syndrome when combined with other serotonergic drugs. Nevertheless, due to the lack of extensive studies on the matter and the fact that ashwagandha appears to affect serotonergic pathways, it would be prudent to exercise caution when combining it with drugs that affect serotonin. [References: - Effects of Withania somnifera (Ashwaga ndha) on Stress and the Stress-Related Neuropsychiatric Disorders Anxiety, Depression, and Insomnia. Curr Neuropharmacol. 2021 Sep 14; 19: 1468–1495. - A Prospective, Randomized Double-Blind, Placebo-Controlled Study of Safety and Efficacy of a High-Concentration Full-Spectrum Extract of Ashwagandha Root in Reducing Stress and Anxiety in Adults. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3573577/]
Bioperine
Anticoagulant/Antiplatelet Drugs
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
In vitro research shows that piperine, a constituent of black pepper, seems to inhibit platelet aggregation. This has not been reported in humans.
Antidiabetes Drugs
Theoretically, black pepper might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Animal research shows that piperine, a constituent of black pepper, can reduce blood glucose levels. Monitor blood glucose levels closely. Dose adjustments might be necessary.
Atorvastatin (Lipitor)
Theoretically, black pepper might increase blood levels of atorvastatin.
Animal research shows that taking piperine, a constituent of black pepper, 35 mg/kg can increase the maximum serum concentration of atorvastatin three-fold. This has not been reported in humans.
Cyclosporine (Neoral, Sandimmune)
Theoretically, black pepper might increase the effects and side effects of cyclosporine.
In vitro research shows that piperine, a constituent of black pepper, increases the bioavailability of cyclosporine. This has not been reported in humans.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
In vitro research suggests that some constituents of black pepper inhibit CYP2D6. This has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
In vitro research and pharmacokinetic simulation data suggest that piperine, a constituent of black pepper, as well as the pepper fruit seem to inhibit CYP3A4. This has not been reported in humans.
Lithium
Theoretically, black pepper might increase blood levels of lithium due to its diuretic effects. The dose of lithium might need to be reduced.
Black pepper is thought to have diuretic properties.
Nevirapine (Viramune)
Black pepper might increase blood levels of nevirapine.
Clinical research shows that piperine, a constituent of black pepper, increases the plasma concentration of nevirapine. However, no adverse effects were observed in this study.
P-Glycoprotein Substrates
Theoretically, black pepper might increase levels of P-glycoprotein substrates.
In vitro research shows that piperine, a constituent of black pepper, seems to inhibit P-glycoprotein.
Pentobarbital (Nembutal)
Theoretically, black pepper might increase the sedative effects of pentobarbital.
Animal research shows that piperine, a constituent of black pepper, increases pentobarbital-induced sleeping time.
Phenytoin (Dilantin)
Black pepper might increase blood levels of phenytoin.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption, slow elimination, and increase levels of phenytoin. Taking a single dose of black pepper 1 gram along with phenytoin seems to double the serum concentration of phenytoin. Consuming a soup with black pepper providing piperine 44 mg/200 mL of soup along with phenytoin also seems to increase phenytoin levels when compared with consuming the same soup without black pepper.
Propranolol (Inderal)
Black pepper might increase blood levels of propranolol.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and slow elimination of propranolol.
Rifampin (Rifadin)
Black pepper might increase blood levels of rifampin.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and serum levels of rifampin.
Theophylline
Black pepper might increase blood levels of theophylline.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and slow elimination of theophylline.
Amoxicillin (Amoxil, Trimox)
Theoretically, black pepper might increase the effects and side effects of amoxicillin.
Animal research shows that taking piperine, a constituent of black pepper, with amoxicillin increases plasma levels of amoxicillin. This has not been reported in humans.
Carbamazepine (Tegretol)
Theoretically, black pepper might increase blood levels of carbamazepine, potentially increasing the effects and side effects of carbamazepine.
One clinical study in patients taking carbamazepine 300 mg or 500 mg twice daily shows that taking a single 20 mg dose of purified piperine, a constituent of black pepper, increases carbamazepine levels. Piperine may increase carbamazepine absorption by increasing blood flow to the GI tract, increasing the surface area of the small intestine, or inhibiting cytochrome P450 3A4 (CYP3A4) in the gut wall. Absorption was significantly increased by 7-10 mcg/mL/hour. The time to eliminate carbamazepine was also increased by 4-8 hours. Although carbamazepine levels were increased, this did not appear to increase side effects. In vitro research also shows that piperine can increase carbamazepine levels by 11% in a time-dependent manner.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
In vitro research suggests that black pepper induces CYP1A2. This has not been reported in humans.
Ginger
Anticoagulant/Antiplatelet Drugs
Ginger may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs. However, research is conflicting.
Laboratory research suggests that ginger inhibits thromboxane synthetase and decreases platelet aggregation. However, this has not been demonstrated unequivocally in humans, with mixed results from clinical trials. Theoretically, excessive amounts of ginger might increase the risk of bleeding when used with anticoagulant/antiplatelet drugs.
Antidiabetes Drugs
Theoretically, taking ginger with antidiabetes drugs might increase the risk of hypoglycemia.
Animal and human research suggests that ginger might increase insulin levels and/or decrease blood glucose levels.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Ginger might increase or decrease the levels of CYP3A4 substrates.
In vitro research and some case reports suggest that ginger inhibits CYP3A4 activity. Three case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking ginger and cancer medications that are CYP3A4 substrates (imatinib, dabrafenib, and crizotinib). However, the causality of this interaction is unclear due to the presence of multiple interacting drugs and routes of administration.
Conversely, other in vitro research suggests that ginger induces CYP3A4 activity, leading to reduced levels of CYP3A4 substrates. However, this interaction has not been reported in humans.
Losartan (Cozaar)
Theoretically, ginger might increase levels of losartan and the risk of hypotension.
In animal research, ginger increased the levels and hypotensive effects of a single dose of losartan. It is not clear if ginger alters the concentration or effects of losartan when taken continuously. Additionally, this interaction has not been shown in humans.
Nifedipine (Procardia)
Ginger may have antiplatelet effects and increase the risk of bleeding if used with nifedipine.
Clinical research shows that combined treatment with ginger 1 gram plus nifedipine 10 mg significantly inhibits platelet aggregation when compared to nifedipine or ginger alone.
P-Glycoprotein Substrates
Ginger might increase the absorption and blood levels of P-glycoprotein (P-gp) substrates.
In vitro research and case reports suggest that ginger inhibits drug efflux by P-gp, potentially increasing absorption and serum levels of P-gp substrates. Two case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking ginger and cancer medications that are P-gp substrates (trametinib, crizotinib). However, the causality of this interaction is unclear due to the presence of multiple interacting drugs and routes of administration.
Phenprocoumon (Marcoumar, Others)
Ginger might increase the risk of bleeding with phenprocoumon.
Phenprocoumon, a warfarin-related anticoagulant, might increase the international normalized ratio (INR) when taken with ginger. There is one case report of a 76-year-old woman with a stable INR on phenprocoumon that increased to greater than 10 when she began consuming dried ginger and ginger tea.
Warfarin (Coumadin)
Ginger might increase the risk of bleeding with warfarin.
Laboratory research suggests that ginger might inhibit thromboxane synthetase and decrease platelet aggregation. In one case report, ginger increased the INR when taken with phenprocoumon, which has similar pharmacological effects as warfarin. In another case report, ginger increased the INR when taken with a combination of warfarin, hydrochlorothiazide, and acetaminophen. A longitudinal analysis suggests that taking ginger increases the risk of bleeding in patients taking warfarin for at least 4 months. However, research in healthy people suggests that ginger has no effect on INR, or the pharmacokinetics or pharmacodynamics of warfarin. Until more is known, monitor INRs closely in patients taking large amounts of ginger.
Calcium Channel Blockers
Theoretically, taking ginger with calcium channel blockers might increase the risk of hypotension.
Some animal and in vitro research suggests that ginger has hypotensive and calcium channel-blocking effects. Another animal study shows that concomitant administration of ginger and the calcium channel blocker amlodipine leads to greater reductions in blood pressure when compared with amlodipine alone.
Cyclosporine (Neoral, Sandimmune)
Theoretically, when taken prior to cyclosporine, ginger might decrease cyclosporine levels.
In an animal model, ginger juice taken 2 hours prior to cyclosporine administration reduced the maximum concentration and area under the curve of cyclosporine by 51% and 40%, respectively. This effect was not observed when ginger juice and cyclosporine were administered at the same time.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, ginger might increase the levels of CYP1A2 substrates.
In vitro research shows that ginger inhibits CYP1A2 activity. However, this interaction has not been reported in humans.
Cytochrome P450 2B6 (Cyp2B6) Substrates
Theoretically, ginger might increase the levels of CYP2B6 substrates.
In vitro research shows that ginger inhibits CYP2B6 activity. However, this interaction has not been reported in humans.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, ginger might increase the levels of CYP2C9 substrates.
In vitro research shows that ginger inhibits CYP2C9 activity. However, this interaction has not been reported in humans.
Metronidazole (Flagyl)
Theoretically, ginger might increase levels of metronidazole.
In an animal model, ginger increased the absorption and plasma half-life of metronidazole. In addition, the elimination rate and clearance of metronidazole was significantly reduced.
Horny Goat Weed
Anticoagulant/Antiplatelet Drugs
Theoretically, horny goat weed might increase the risk of bleeding.
In vitro research and animal research shows that horny goat weed can inhibit platelet aggregation and thrombus formation. This effect has not been reported in humans.
Antihypertensive Drugs
Theoretically, horny goat weed might increase the risk of hypotension.
Laboratory research suggests that horny goat weed might have hypotensive effects. This effect has not been reported in humans.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, horny goat weed might increase the effects and side effects of CYP1A2 substrates.
In vitro, horny goat weed leaf extract inhibits CYP1A2. This effect has not been reported in humans.
Cytochrome P450 2B6 (Cyp2B6) Substrates
Theoretically, horny goat weed might increase the effects and side effects of CYP2B6 substrates.
In vitro, horny goat weed leaf extract inhibits CYP2B6. This effect has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, horny goat weed might increase the effects and side effects of CYP3A4 substrates.
In vitro, horny goat weed extract inhibits CYP3A4 and suppresses CYP3A4 mRNA expression. This effect has not been reported in humans.
Estrogens
Theoretically, concomitant use of horny goat weed with estrogens might increase their therapeutic and adverse effects.
In vitro evidence suggests that horny goat weed has estrogenic activity. In clinical research, horny goat weed has been shown to increase blood levels of estrogen in some females.
Vitamin B3
Alcohol (Ethanol)
Concomitant use of alcohol and niacin might increase the risk of flushing and hepatotoxicity.
Alcohol can exacerbate the flushing and pruritus associated with niacin. Large doses of niacin might also exacerbate liver dysfunction associated with chronic alcohol use. A case report describes delirium and lactic acidosis in a patient taking niacin 3 grams daily who ingested 1 liter of wine. Advise patients to avoid large amounts of alcohol while taking niacin.
Allopurinol (Zyloprim)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as allopurinol.
Large doses of niacin can reduce urinary excretion of uric acid, potentially resulting in hyperuricemia. Doses of uricosurics such as allopurinol might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Anticoagulant/Antiplatelet Drugs
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Several cases of clotting factor synthesis deficiency and coagulopathy have been reported in patients taking sustained-release niacin. Also, thrombocytopenia has been reported in patients treated with niacin or niacin plus lovastatin.
Antidiabetes Drugs
Niacin can increase blood glucose levels and may diminish the effects of antidiabetes drugs.
Niacin impairs glucose tolerance in a dose-dependent manner, probably by causing or aggravating insulin resistance and increasing hepatic production of glucose. In diabetes patients, niacin 4.5 grams daily for 5 weeks can increase plasma glucose by an average of 16% and glycated hemoglobin (HbA1c) by 21%. However, lower doses of 1.5 grams daily or less appear to have minimal effects on blood glucose. In some patients, glucose levels increase when niacin is started, but then return to baseline when a stable dose is reached. Up to 35% of patients with diabetes may need adjustments in hypoglycemic therapy when niacin is added.
Antihypertensive Drugs
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
The vasodilating effects of niacin can cause hypotension. Furthermore, some clinical evidence suggests that a one-hour infusion of niacin can reduce systolic, diastolic, and mean blood pressure in hypertensive patients. This effect is not observed in normotensive patients.
Bile Acid Sequestrants
Bile acid sequestrants can bind niacin and decrease absorption. Separate administration by 4-6 hours to avoid an interaction.
In vitro studies show that colestipol (Colestid) binds about 98% of available niacin and cholestyramine (Questran) binds 10% to 30%.
Gemfibrozil (Lopid)
Theoretically, concomitant use of niacin and gemfibrozil might increase the risk of myopathy in some patients.
A case of myopathy from concomitant use of niacin and gemfibrozil has been reported. Niacin alone has also been associated with cases of myopathy. Using gemfibrozil with niacin might further increase the risk of developing myopathy.
Hepatotoxic Drugs
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Niacin has been associated with cases of liver toxicity, especially when used in pharmacologic doses. Sustained-release niacin preparations appear to be associated with a higher risk of hepatotoxicity than immediate-release niacin.
Hmg-Coa Reductase Inhibitors ("Statins")
Theoretically, concomitant use of niacin and statins might increase the risk of myopathy and rhabdomyolysis in some patients.
Some case reports have raised concerns that niacin might increase the risk of myopathy and rhabdomyolysis when combined with statins. However, a significantly increased risk of myopathy has not been demonstrated in clinical trials, including those using an FDA-approved combination of lovastatin and niacin (Advicor).
Probenecid (Benemid)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as probenecid.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as probenecid might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Sulfinpyrazone (Anturane)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as sulfinpyrazone.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as sulfinpyrazone might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Thyroid Hormone
Theoretically, niacin might antagonize the therapeutic effects of thyroid hormones.
Clinical research and case reports suggests that taking niacin can reduce serum levels of thyroxine-binding globulin by up to 25% and moderately reduce levels of thyroxine (T4). Patients taking thyroid hormone for hypothyroidism might need dose adjustments when using niacin.
Transdermal Nicotine (Nicoderm)
Theoretically, concomitant use of niacin and transdermal nicotine might increase the risk of flushing and dizziness.
Niacin and nicotine can both cause flushing and dizziness.
Warfarin (Coumadin)
There is limited evidence that niacin may increase the anticoagulant effects of warfarin.
In a case report, a patient on warfarin developed an elevated international normalized ratio (INR) of 3.9 after taking niacin for two weeks. The patient's INR was previously stable, ranging between 2 and 3 in recent months, and no other medication changes were identified. The elevated INR returned to therapeutic range within 4 days following the discontinuation of niacin.
Aspirin
Large doses of aspirin might alter the clearance of niacin.
Aspirin is often used with niacin to reduce niacin-induced flushing. Doses of 80-975 mg aspirin have been used, but 325 mg appears to be optimal. Aspirin also seems to reduce the clearance of niacin by competing for glycine conjugation. Taking aspirin 1 gram seems to reduce niacin clearance by 45%. This is probably a dose-related effect and not clinically significant with the more common aspirin dose of 325 mg.
L-Arginine
Ace Inhibitors (Aceis)
Theoretically, concomitant use of L-arginine and ACE inhibitors may increase the risk for hypotension and hyperkalemia.
Combining L-arginine with some antihypertensive drugs, especially ACE inhibitors, seems to have additive vasodilating and blood pressure-lowering effects. Furthermore, ACE inhibitors can increase potassium levels. Use of L-arginine has been associated with hyperkalemia in some patients. Theoretically, concomitant use of ACE inhibitors with L-arginine may increases the risk of hyperkalemia.
Angiotensin Receptor Blockers (Arbs)
Theoretically, concomitant use of L-arginine and ARBs may increase the risk of hypotension and hyperkalemia.
L-arginine increases nitric oxide, which causes vasodilation. Combining L-arginine with ARBs seems to increase L-arginine-induced vasodilation. Furthermore, ARBs can increase potassium levels. Use of L-arginine has been associated with hyperkalemia in some patients. Theoretically, concomitant use of ARBs with L-arginine may increases the risk of hyperkalemia.
Anticoagulant/Antiplatelet Drugs
Theoretically, concomitant use of L-arginine with anticoagulant and antiplatelet drugs might have additive effects and increase the risk of bleeding.
Preliminary research suggests that L-arginine infusions reduce platelet aggregation in humans. The clinical significance of this effect is unclear.
Antidiabetes Drugs
Theoretically, concomitant use of L-arginine might have additive effects with antidiabetes drugs.
Preliminary clinical research shows that L-arginine decreases blood glucose levels in patients with type 2 diabetes.
Antihypertensive Drugs
Theoretically, concomitant use of L-arginine and antihypertensive drugs may increase the risk of hypotension.
L-arginine increases nitric oxide, which causes vasodilation. Clinical evidence shows that L-arginine can reduce blood pressure in some individuals with hypertension. Furthermore, combining L-arginine with some antihypertensive drugs seems to have additive vasodilating and blood pressure-lowering effects.
Isoproterenol (Isuprel)
Theoretically, concurrent use of isoproterenol and L-arginine might result in additive effects and hypotension.
Preliminary clinical evidence suggests that L-arginine enhances isoproterenol-induced vasodilation in patients with essential hypertension or a family history of essential hypertension.
Potassium-Sparing Diuretics
Theoretically concomitant use of potassium-sparing diuretics with L-arginine may increases the risk of hyperkalemia.
Potassium-sparing diuretics can increase potassium levels. Use of L-arginine has been associated with hyperkalemia in some patients.
Sildenafil (Viagra)
Theoretically, concurrent use of sildenafil and L-arginine might increase the risk for hypotension.
In vivo, concurrent use of L-arginine and sildenafil has resulted in increased vasodilation. Theoretically, concurrent use might have additive vasodilatory and hypotensive effects. However, in studies evaluating the combined use of L-arginine and sildenafil for erectile dysfunction, hypotension was not reported.
Testosterone
Theoretically, concomitant use of L-arginine and testosterone might have additive effects.
In clinical research, L-arginine increases the level of testosterone in male patients with erectile dysfunction. The clinical significance of this finding is unclear.
Vitamin A
Retinoids
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Retinoids, which are vitamin A derivatives, could have additive toxic effects when taken with vitamin A supplements.
Hepatotoxic Drugs
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
The tolerable upper intake level (UL) is the highest level of intake that is likely to pose no risk of adverse effects. Doses of vitamin A above the UL can cause hepatotoxicity, ranging from elevated liver enzymes to liver failure.
Tetracycline Antibiotics
Theoretically, taking tetracycline antibiotics with high doses of vitamin A can increase the risk of pseudotumor cerebri.
Benign intracranial hypertension (pseudotumor cerebri) can occur with tetracyclines and with acute or chronic vitamin A toxicity. Case reports suggest that taking tetracyclines and vitamin A concurrently can increase the risk of this condition. Avoid high doses of vitamin A in people taking tetracyclines chronically.
Warfarin (Coumadin)
Theoretically, high doses of vitamin A could increase the risk of bleeding with warfarin.
Vitamin A toxicity is associated with hemorrhage and hypoprothrombinemia, possibly due to vitamin K antagonism. Advise patients taking warfarin to avoid doses of vitamin A above the tolerable upper intake level of 10,000 IU/day for adults.
Sea Buckthorn Fruit Oil
Anticoagulant/Antiplatelet Drugs
Theoretically, sea buckthorn may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Clinical research suggests that sea buckthorn fruit extracts can inhibit platelet aggregation and adhesion to collagen and fibrinogen.
Antihypertensive Drugs
Theoretically, taking sea buckthorn with antihypertensive drugs might increase the risk of hypotension.
Taking sea buckthorn appears to reduce blood pressure in some patients.
Tribulus terrestris
Antidiabetes Drugs
Taking tribulus with antidiabetes drugs might increase the risk of hypoglycemia.
Clinical research shows that Tribulus can lower blood glucose levels in adults with type 2 diabetes who are taking antidiabetes medications.
Antihypertensive Drugs
Theoretically, taking tribulus with antihypertensive drugs might increase the risk of hypotension.
Animal research shows that tribulus can lower blood pressure by inhibiting angiotensin-converting enzyme (ACE). Tribulus has also demonstrated hypotensive effects in pre-hypertensive adults.
Lithium
Theoretically, tribulus might increase the levels and clinical effects of lithium.
Tribulus is thought to have diuretic properties. Due to these potential diuretic effects, tribulus might reduce excretion and increase levels of lithium. The dose of lithium might need to be decreased.
Vitamin B6
Amiodarone (Cordarone)
Theoretically, vitamin B6 might increase the photosensitivity caused by amiodarone.
Despite initial case reports suggesting that pyridoxine may have a protective effect against amiodarone-induced photosensitivity, preliminary clinical research suggests that pyridoxine may actually exacerbate this adverse effect.
Antihypertensive Drugs
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Research in hypertensive rats shows that vitamin B6 can decrease systolic blood pressure. Similarly, clinical research in patients with hypertension shows that taking high doses of vitamin B6 may reduce systolic and diastolic blood pressure, possibly by reducing plasma levels of epinephrine and norepinephrine.
Phenobarbital (Luminal)
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenobarbital, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenobarbital to avoid high doses of vitamin B6.
Phenytoin (Dilantin)
High doses of vitamin B6 may reduce the levels and clinical effects of phenytoin.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenytoin, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenytoin to avoid high doses of vitamin B6.
Levodopa
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Vitamin B6 (pyridoxine) enhances the metabolism of levodopa, reducing its clinical effects. However, this interaction does not occur when carbidopa is used concurrently with levodopa (Sinemet). Therefore, it is not likely to be a problem in most people.
Mucuna pruriens Seed Extract
Levodopa
Concomitant use can increase the risk of levodopa-related adverse effects.
Cowhage contains levodopa. Some cowhage products have been standardized to contain 75-400 mg of levodopa per dose.
Methyldopa (Aldomet)
Theoretically, concomitant use of cowhage and methyldopa might increase the risk of hypotension.
Cowhage contains levodopa. Use of levodopa with methyldopa might cause additive hypotension. In addition, methyldopa may inhibit peripheral decarboxylation of levodopa and increase levodopa levels in the central nervous system; avoid using.
Monoamine Oxidase Inhibitors (Maois)
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Cowhage contains levodopa. Use of levodopa with non-selective MAOIs might cause hypertensive crisis. However, this interaction has not been reported with MAO-B selective inhibitors such as selegiline.
Anesthesia
Theoretically, concomitant use of cowhage and anesthesia might increase the risk of arrhythmias.
Cowhage contains levodopa. Use of levodopa with cyclopropane or halogenated hydrocarbon anesthesia has led to arrhythmias. Other anesthetics have not been implicated. Use other anesthetics in patients taking cowhage or tell patients to stop taking cowhage at least 2 weeks before surgery.
Antidiabetes Drugs
Theoretically, concomitant use of cowhage and antidiabetes drugs might increase the risk of hypoglycemia.
Animal research shows that cowhage might have hypoglycemic effects.
Antipsychotic Drugs
Theoretically, use of cowhage might decrease the clinical effects of antipsychotic drugs.
Cowhage contains levodopa. Use of levodopa might counteract the antidopaminergic effects of antipsychotic medications.
Guanethidine (Ismelin)
Theoretically, concomitant use of cowhage and guanethidine might increase the risk of hypotension.
Cowhage contains levodopa. Use of levodopa with guanethidine might cause additive hypotension; avoid using.
Tricyclic Antidepressants (Tcas)
Theoretically, use of TCAs might reduce the levels and clinical effects of cowhage.
Cowhage contains levodopa. Use of TCAs might reduce the absorption of levodopa. Some case reports describe patients that developed hypertension and dyskinesia when taking both levodopa and TCAs.
Angelica sinensis
Warfarin (Coumadin)
Dong quai may increase the risk of bleeding when used with warfarin.
Case reports suggest that concomitant use of dong quai with warfarin can increase the anticoagulant effects of warfarin and increase the risk of bleeding. In one case, after 4 weeks of taking dong quai 565 mg once or twice daily, the international normalized ratio (INR) increased to 4.9. The INR normalized 4 weeks after discontinuation of dong quai.
Anticoagulant/Antiplatelet Drugs
Theoretically, dong quai may increase the risk of bleeding when used with anticoagulant or antiplatelet drugs; however, research is conflicting.
Animal studies suggest that dong quai has antithrombin activity and inhibits platelet aggregation due to its coumarin components. Additionally, some case reports in humans suggest that dong quai can increase the anticoagulant effects of warfarin. However, clinical research in healthy adults shows that taking 1 gram of dong quai root daily for 3 weeks does not significantly inhibit platelet aggregation or cause bleeding. Until more is known, use dong quai with caution in patients taking antiplatelet/anticoagulant drugs.
Estrogens
Theoretically, dong quai may reduce the effects of estrogens.
Dong quai has estrogenic effects. Theoretically, concomitant use of large amounts of dong quai might interfere with hormone replacement therapy due to competition for estrogen receptors.
Damiana
Antidiabetes Drugs
Theoretically, taking damiana with antidiabetes drugs might increase the risk of hypoglycemia.
Animal research shows that taking damiana lowers blood glucose level.
Asparagus
Diuretic Drugs
Theoretically, asparagus root might increase diuresis and electrolyte loss when used with diuretic drugs.
Animal studies show that asparagus root extracts have diuretic effects. This effect has not been reported in humans.
Lithium
Theoretically, asparagus root might cause diuresis, reducing lithium clearance.
Animal studies show that asparagus root extracts have diuretic effects. Theoretically, this might reduce excretion and increase levels of lithium. The dose of lithium might need to be decreased.
Zinc
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Theoretically, zinc might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after zinc containing products.
Cephalexin (Keflex)
Zinc might decrease cephalexin levels by chelating with cephalexin in the gut and preventing its absorption.
A pharmacokinetic study shows that zinc sulfate 250 mg taken concomitantly with cephalexin 500 mg decreases peak levels of cephalexin by 31% and reduces the exposure to cephalexin by 27%. Also, taking zinc sulfate 3 hours before cephalexin decreases peak levels of cephalexin by 11% and reduces the exposure to cephalexin by 18%. By decreasing cephalexin levels, zinc might increase the risk of treatment failure. This effect does not occur when zinc is taken 3 hours after the cephalexin dose. To avoid an interaction, advise patients take zinc sulfate 3 hours after taking cephalexin.
Cisplatin (Platinol-Aq)
Theoretically, zinc might interfere with the therapeutic effects of cisplatin.
Animal research suggests that zinc stimulates tumor cell production of the protein metallothionein, which binds and inactivates cisplatin. It is not known whether zinc supplements or high dietary zinc intake can cause clinically significant interference with cisplatin therapy. Cisplatin might also increase zinc excretion.
Integrase Inhibitors
Theoretically, taking zinc along with integrase inhibitors might decrease the levels and clinical effects of these drugs.
Zinc is a divalent cation. Pharmacokinetic studies have shown that other divalent cations such as calcium and iron can decrease blood levels of the integrase inhibitor dolutegravir through chelation.
Penicillamine (Cuprimine, Depen)
Zinc might reduce the levels and clinical effects of penicillamine.
By forming an insoluble complex with penicillamine, zinc interferes with penicillamine absorption and activity. Zinc supplements reduce the efficacy of low-dose penicillamine (0.5-1 gram/day), but do not seem to affect higher doses (1-2.75 gram/day), provided dosing times are separated. Advise patients to take zinc and penicillamine at least 2 hours apart.
Quinolone Antibiotics
Zinc can decrease the levels and clinical effects of quinolones antibiotics.
Quinolones form complexes with zinc in the gastrointestinal tract, reducing absorption of both the quinolone and zinc if taken at the same time. Advise patients to take these drugs at least 2 hours before, or 4-6 hours after, zinc supplements.
Ritonavir (Norvir)
Zinc modestly reduces levels of ritonavir.
Clinical research shows that zinc might reduce serum ritonavir levels by chelating with ritonavir in the gut and preventing its absorption. In patients with HIV, ritonavir is taken with atazanavir to prevent the metabolism and increase the effects of atazanavir. A pharmacokinetic study shows that, in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate (Solvazinc tablets) 125 mg as a single dose or as multiple daily doses for 2 weeks reduces plasma levels of ritonavir by about 16%. However, atazanavir levels still remains high enough to prevent HIV virus replication. Therefore, the decrease in ritonavir levels is not likely to be clinically significant.
Tetracycline Antibiotics
Zinc might reduce levels of tetracycline antibiotics.
Tetracyclines form complexes with zinc in the gastrointestinal tract, which can reduce absorption of both the tetracycline and zinc when taken at the same time. Taking zinc sulfate 200 mg with tetracycline reduces absorption of the antibiotic by 30% to 40%. Demeclocycline and minocycline cause a similar interaction. However, doxycycline does not seem to interact significantly with zinc. Advise patients to take tetracyclines at least 2 hours before, or 4-6 hours after, zinc supplements to avoid any interactions.
Amiloride (Midamor)
Amiloride can modestly reduce zinc excretion and increase zinc levels.
Clinical research shows that amiloride can reduce urinary zinc excretion, especially at doses of 10 mg per day or more. This zinc-sparing effect can help to counteract zinc losses caused by thiazide diuretics, but it is unlikely to cause zinc toxicity at usual amiloride doses. The other potassium-sparing diuretics, spironolactone (Aldactone) and triamterene (Dyrenium), do not seem to have a zinc-sparing effect.
Atazanavir (Reyataz)
Zinc modestly reduces levels of atazanavir, although this effect does not seem to be clinically significant.
Clinical research shows that zinc might decrease serum atazanavir levels by chelating with atazanavir in the gut and preventing its absorption. Although a single dose of zinc sulfate (Solvazinc tablets) 125 mg orally does not affect atazanavir concentrations in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate 125 mg daily for 2 weeks reduces plasma levels of atazanavir by about 22% in these patients. However, despite this decrease, atazanavir levels still remain at high enough concentrations for the prevention of HIV virus replication.
L-Tyrosine
Levodopa
Theoretically, tyrosine might decrease the effectiveness of levodopa.
Tyrosine and levodopa compete for absorption in the proximal duodenum by the large neutral amino acid (LNAA) transport system. Advise patients to separate doses of tyrosine and levodopa by at least 2 hours.
Thyroid Hormone
Theoretically, tyrosine might have additive effects with thyroid hormone medications.
Tyrosine is a precursor to thyroxine and might increase levels of thyroid hormones.
Vitamin B12
Metformin (Glucophage)
Metformin, a common medication used to manage type 2 diabetes, has been associated with lower vitamin B12 levels in some individuals. Prolonged use of metformin can interfere with the absorption of B12 in the digestive system, potentially leading to a deficiency in this essential vitamin.
Sarsaparilla
Digoxin (Lanoxin)
Theoretically, concomitant use of sarsaparilla with digoxin might increase the risk of cardiac toxicity.
Sarsaparilla is thought to have diuretic properties, which could potentially cause potassium loss. Overuse or misuse of sarsaparilla with cardiac glycoside therapy might increase the risk of cardiac toxicity due to potassium loss.
Lithium
Theoretically, sarsaparilla might increase the effects and adverse effects of lithium.
Sarsaparilla is thought to have diuretic properties. Due to these effects, sarsaparilla might reduce excretion and increase levels of lithium. The dose of lithium might need to be decreased.
Brand information
Manufacturer and brand details for LeptiCell, from the product label.
PhytAge Labs
See all PhytAge Labs products- Name
- PhytAge Laboratories
- Street Address
- 19655 E 35th Dr, Suite 100
- City
- Aurora
- State
- CO
- ZipCode
- 80011
- Phone Number
- 1-800-822-5753
LeptiCell by PhytAge Labs: Common Questions
Does LeptiCell by PhytAge Labs interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Is LeptiCell safe to take if I'm pregnant?
Can I take LeptiCell while breastfeeding?
What does LeptiCell do?
Will LeptiCell interact with my blood pressure medicine?
Can I take LeptiCell with my diabetes medication?
What are the most common side effects?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if LeptiCell is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind LeptiCell’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin B6
Interacts with 210 drugsVitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is best known for helping with pregnancy-rel...
Read the full Vitamin B6 monograph → Herb & supplement monographVitamin B12
Interacts with 20 drugsVitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very helpful for people who are deficient — su...
Read the full Vitamin B12 monograph → Herb & supplement monographL-arginine
Interacts with 403 drugsL-arginine is an amino acid that the body uses to make nitric oxide, a substance that helps blood vessels relax and widen. It is popularly used for blood pressure, erectile dysfunction, and...
Read the full L-arginine monograph → Herb & supplement monographTyrosine
Interacts with 21 drugsL-tyrosine is an amino acid your body uses to make brain chemicals like dopamine and norepinephrine. Some studies suggest it may help mental performance during short-term stress, sleep loss,...
Read the full Tyrosine monograph → Herb & supplement monographZinc
Interacts with 67 drugsZinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but supplements can help correct or prevent a defici...
Read the full Zinc monograph → Herb & supplement monographBlack Pepper
Interacts with 1,019 drugsBlack pepper is a common kitchen spice that is generally safe in the amounts used in food. Its extract, piperine, is mostly added to supplements to help the body absorb other ingredients (li...
Read the full Black Pepper monograph → Herb & supplement monographNiacin
Interacts with 727 drugsNiacin (vitamin B3) is an essential nutrient your body needs for energy and metabolism, and deficiency is uncommon in most developed countries. Prescription-strength niacin has been used to...
Read the full Niacin monograph → Herb & supplement monographMaca
Maca is a nutrient-rich Andean root often used for energy, libido, and menopause symptoms. Early studies suggest it may modestly help sexual desire and some menopause symptoms, but the evide...
Read the full Maca monograph → Herb & supplement monographTribulus
Interacts with 259 drugsTribulus is a plant supplement most often marketed to boost libido, testosterone, and athletic performance, but the human evidence behind these claims is weak and inconsistent. It is general...
Read the full Tribulus monograph → Herb & supplement monographAsparagus
Interacts with 76 drugsAsparagus is a nutritious vegetable that is safe and healthy to eat as part of a normal diet. Most of its claimed medicinal benefits, such as use as a diuretic or for urinary health, come fr...
Read the full Asparagus monograph → Herb & supplement monographGinger
Interacts with 1,007 drugsGinger is a widely used culinary spice with a long history in traditional medicine, and it has the strongest evidence for helping with nausea and vomiting, including from motion sickness, pr...
Read the full Ginger monograph → Herb & supplement monographDamiana
Interacts with 86 drugsDamiana is a traditional herb most famous as an aphrodisiac and mild mood-lifter, but solid human evidence for any of its uses is very limited. It is generally well tolerated in the small am...
Read the full Damiana monograph → Herb & supplement monographDong Quai
Interacts with 163 drugsDong Quai is a traditional Chinese herb often called "female ginseng" and is mostly used for menstrual and menopausal complaints. High-quality scientific evidence that it works for these use...
Read the full Dong Quai monograph → Herb & supplement monographVitamin A
Interacts with 387 drugsVitamin A is an essential nutrient important for vision, skin, immune function, and growth. Most people get enough from a balanced diet, and supplements are mainly useful for correcting a tr...
Read the full Vitamin A monograph → Herb & supplement monographCowhage
Interacts with 193 drugsCowhage (Mucuna pruriens) is a tropical legume best known as a natural source of L-dopa, the compound the body turns into dopamine. It is most studied for Parkinson's disease symptoms and ma...
Read the full Cowhage monograph → Herb & supplement monographMuira Puama
Muira puama is a Brazilian plant traditionally used as an aphrodisiac and general tonic, often nicknamed 'potency wood.' Human research is very limited, so its benefits are not well proven,...
Read the full Muira Puama monograph → Herb & supplement monographSarsaparilla
Interacts with 2 drugsSarsaparilla is a traditional root used in teas, tonics, and old-fashioned root beer flavoring. Modern evidence for its health claims is very limited and comes mostly from lab studies, so it...
Read the full Sarsaparilla monograph → Herb & supplement monographPantothenic Acid
Pantothenic acid is vitamin B5, an essential nutrient your body uses to turn food into energy. True deficiency is very rare because it is found in nearly all foods, and most people meet thei...
Read the full Pantothenic Acid monograph → Herb & supplement monographAshwagandha
Interacts with 1,372 drugsAshwagandha is an Ayurvedic herb most often taken to help with stress, anxiety, and sleep, and some small studies suggest it may help, though the evidence is still limited. It is generally w...
Read the full Ashwagandha monograph → Herb & supplement monographCatuaba
Catuaba is a Brazilian herbal bark long used as a traditional aphrodisiac and energy tonic, but there is very little reliable human research to show it works for any health condition. Qualit...
Read the full Catuaba monograph → Herb & supplement monographSea Buckthorn
Interacts with 289 drugsSea buckthorn is a berry-bearing shrub rich in vitamins, carotenoids, and fatty acids that people use for skin, eye, digestive, and heart health. Early research is promising for a few uses l...
Read the full Sea Buckthorn monograph → Herb & supplement monographHorny Goat Weed
Interacts with 963 drugsHorny goat weed (Epimedium) is a traditional Chinese herb most often marketed for low libido and erectile problems, but solid human evidence for these uses is lacking. While short-term use s...
Read the full Horny Goat Weed monograph →Sources & How We Checked
LeptiCell's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 534 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Vitamin B6 32 references
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Geerling BJ, Dagnelie PC, Badart-Smook A, et al. Diet as a risk factor for the development of ulcerative colitis. Am J Gastroenterol 2000;95:1008-13. PubMed
- South M. Neonatal seizures after pyridoxine use -- reply. Lancet 1999;354:2083. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Baxter P, Aicardi J. Neonatal seizures after pyridoxine use. Lancet 1999;354:2082-3. PubMed
- Bendich A, Cohen M. Vitamin B6 safety issues. Ann N Y Acad Sci 1990;585:321-30.
- Schaumburg H, Kaplan J, Windebank A. Sensory neuropathy from pyridoxine abuse. A new megavitamin syndrome. N Engl J Med 1983;309:445-8. PubMed
- Gordon N. Pyridoxine dependency: an update. Dev Med Child Neurol 1997;39:63-5. PubMed
- Lewis PJ. Pain in the hand and wrist. Pyridoxine supplements may help patients with carpal tunnel syndrome. BMJ 1995;310:1534. PubMed
- Kaufman G. Pyridoxine against amiodarone-induced photosensitivity (letter). Lancet 1984;1:51-2. PubMed
- Mulrow JP, Mulrow CD, McKenna WJ. Pyridoxine and amiodarone-induced photosensitivity. Ann Intern Med 1985;103:68-9. PubMed
- Kawada A, Kashima A, Shiraishi H, et al. Pyridoxine-induced photosensitivity and hypophosphatasia. Dermatology 2000;201:356-60.. PubMed
- Vasile A, Goldberg R, Kornberg B. Pyridoxine toxicity: report of a case. J Am Osteopath Assoc 1984;83:790-1. DOI
- Hansson O, Sillanpaa M. Pyridoxine and serum concentration of phenytoin and phenobarbitone. Lancet 1976;1:256. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Chittumma P, Kaewkiattikun K, Wiriyasiriwach B. Comparison of the effectiveness of ginger and vitamin B6 for treatment of nausea and vomiting in early pregnancy: a randomized double-blind controlled trial. J Med Assoc Thai 2007;90:15-20.
- Hatzitolios, A., Iliadis, F., Katsiki, N., and Baltatzi, M. Is the anti-hypertensive effect of dietary supplements via aldehydes reduction evidence based? A systematic review. Clin Exp.Hypertens. 2008;30(7):628-639. PubMed
- Vasdev, S., Ford, C. A., Parai, S., Longerich, L., and Gadag, V. Dietary vitamin B6 supplementation attenuates hypertension in spontaneously hypertensive rats. Mol.Cell Biochem. 1999;200(1-2):155-162.
- de, Vogel S., Dindore, V., van, Engeland M., Goldbohm, R. A., van den Brandt, P. A., and Weijenberg, M. P. Dietary folate, methionine, riboflavin, and vitamin B-6 and risk of sporadic colorectal cancer. J Nutr 2008;138(12):2372-2378. PubMed
- Hagen, I., Nesheim, B. I., and Tuntland, T. No effect of vitamin B-6 against premenstrual tension. A controlled clinical study. Acta Obstet.Gynecol.Scand. 1985;64(8):667-670. PubMed
- Aybak, M., Sermet, A., Ayyildiz, M. O., and Karakilcik, A. Z. Effect of oral pyridoxine hydrochloride supplementation on arterial blood pressure in patients with essential hypertension. Arzneimittelforschung. 1995;45(12):1271-1273.
- Lal, K. J., Dakshinamurti, K., and Thliveris, J. The effect of vitamin B6 on the systolic blood pressure of rats in various animal models of hypertension. J Hypertens. 1996;14(3):355-363. PubMed
- Lauritzen CH, Reuter HD, Repges R, Bohnert K, and Schmidt U. Treatment of premenstrual tension syndrome with Vitex agnus castus. Controlled, double-blind study versus pyridoxine. Phytomed 1997;4(3):183-189. PubMed
- Fonseca VA, Lavery LA, Thethi TK, et al. Metanx in type 2 diabetes with peripheral neuropathy: A randomized trial. Am J Med 2013;126(2):141-9. PubMed
- Hankey GJ, Eikelboom JW, Yi Q, et al. Treatment with B vitamins and incidence of cancer in patients with previous stroke or transient ischemic attack: Results of a randomized placebo-controlled trial. Stroke 2012;43(6):1572-7. PubMed
- Hoyer-Kuhn H, Kohbrok S, Volland R, Franklin J, Hero B, Beck BB, Hoppe B. Vitamin B6 in primary hyperoxaluria I: first prospective trial after 40 years of practice. Clin J Am Soc Nephrol. 2014 Mar;9(3):468-77. PubMed
- Mahmoud A, Tabassum S, Al Enazi S, et al. Amelioration of levetiracetam-induced behavioral side effects by pyridoxine. A randomized double blind controlled study. Pediatr Neurol 2021;119:15-21. PubMed
- Gupta M, Gallante B, Bamberger JN, et al. Prospective randomized evaluation of idiopathic hyperoxaluria treatments. J Endourol 2021;35(12):1844-1851. PubMed
- Li H, Chen M, Liang S, et al. Excessive vitamin B6 during treatment is related to poor prognosis of patients with nasopharyngeal carcinoma: A U-shaped distribution suggests low dose supplement. Clin Nutr 2021;40(4):2293-2300. PubMed
- Tanigawa J, Nabatame S, Tominaga K, et al. High-dose pyridoxine treatment for inherited glycosylphosphatidylinositol deficiency. Brain Dev 2021;43(6):680-687. PubMed
- Committee on Practice Bulletins-Obstetrics. ACOG Practice Bulletin No. 189: Nausea And Vomiting Of Pregnancy. Obstet Gynecol. 2018;131(1):e15-e30. PubMed
Vitamin B12 30 references
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Hartman TJ, Woodson K, Stolzenberg-Solomon R, et al. Association of the B-vitamins pyridoxal 5'-phosphate (B6), B12, and folate with lung cancer risk in older men. Am J Epidemiol 2001;153:688-94.. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Lange H, Suryapranata H, De Luca G, et al. Folate therapy and in-stent restenosis after coronary stenting. N Engl J Med 2004;350:2673-81. PubMed
- Collin, S. M., Metcalfe, C., Refsum, H., Lewis, S. J., Zuccolo, L., Smith, G. D., Chen, L., Harris, R., Davis, M., Marsden, G., Johnston, C., Lane, J. A., Ebbing, M., Bonaa, K. H., Nygard, O., Ueland, P. M., Grau, M. V., Baron, J. A., Donovan, J. L., Nea
- Geissbuhler, P., Mermillod, B., and Rapin, C. H. Elevated serum vitamin B12 levels associated with CRP as a predictive factor of mortality in palliative care cancer patients: a prospective study over five years. J.Pain Symptom.Manage. 2000;20(2):93-103. PubMed
- Salles, N., Herrmann, F., Sakbani, K., Rapin, C. H., and Sieber, C. High vitamin B12 level: a strong predictor of mortality in elderly inpatients. J Am Geriatr.Soc 2005;53(5):917-918.
- Looker, H. C., Fagot-Campagna, A., Gunter, E. W., Pfeiffer, C. M., Sievers, M. L., Bennett, P. H., Nelson, R. G., Hanson, R. L., and Knowler, W. C. Homocysteine and vitamin B(12) concentrations and mortality rates in type 2 diabetes. Diabetes Metab Res R
- Uhl, W., Nolting, A., Golor, G., Rost, K. L., and Kovar, A. Safety of hydroxocobalamin in healthy volunteers in a randomized, placebo-controlled study. Clin Toxicol (Phila) 2006;44 Suppl 1:17-28. PubMed
- Borron, S. W., Baud, F. J., Barriot, P., Imbert, M., and Bismuth, C. Prospective study of hydroxocobalamin for acute cyanide poisoning in smoke inhalation. Ann Emerg.Med 2007;49(6):794-801, 801. PubMed
- Borron, S. W., Baud, F. J., Megarbane, B., and Bismuth, C. Hydroxocobalamin for severe acute cyanide poisoning by ingestion or inhalation. Am J Emerg.Med 2007;25(5):551-558. PubMed
- Lewis, J. G. Gout, Steatorrhoea, and Megaloblastic Anaemia. Ann Rheum.Dis 1962;21(3):284-286. PubMed
- Tal, S., Shavit, Y., Stern, F., and Malnick, S. Association between vitamin B12 levels and mortality in hospitalized older adults. J Am Geriatr.Soc 2010;58(3):523-526. PubMed
- Baztan, J. J., Gavidia, J. J., Gomez-Pavon, J., Esteve, A., and Ruiperez, I. High vitamin B12 levels and in-hospital mortality. J Am Geriatr.Soc 2010;58(11):2237-2238. PubMed
- Omboni, E., Checchini, M., and Longoni, F. [Hypopotassemia and megaloblastic anemia. Presentation of a case]. Minerva Med 8-31-1987;78(16):1255-1257.
- Aalfs As, Scholvinck LH, Horvath B. Acneiform eruption in a 5-year old due to vitamin B12 supplementation. Eur J Dermatol 2013;23(5):726-7. PubMed
- Balta I, Ozuguz P. Vitamin B12-induced acneiform eruption. Cutan Ocul Toxicol 2014;33(2):94-5. PubMed
- Carman KB, Belgemen T, Yis U. Involuntary movements misdiagnosed as seizure during vitamin B12 treatment. Pediatr Emerg Care 2013;29(11):1223-4. PubMed
- Djuric V, Bogic M, Popadic AP, et al. Anaphylactic reaction to hydroxycobalamin with tolerance to cyanocobalamin. Ann Allergy Asthma Immunol 2012;108(3):207-8. PubMed
- Kartel O, Gulec M, Demirel F, et al. Vitamin B12 allergy and successful desensitization with cyanocobalamin: A case report. Allergol Immunopath (Madr) 2012;40(5):324-5.
- Patiroglu T, Unal E, Yildirim S. Infantile tremor syndrome associated with cobalamin therapy: A case report. Clin Neurol Neurosurg 2013;115(9):1903-5. PubMed
- Schulte S, Barkema LW, Kardaun SH. Long-lasting atypical acneiform eruption with prominent comedones induced by hydroxocobalamin (vitamin B12). J Dtsch Dermatol Ges 2014;12(6):502-3.
- Zanus C, Alberini E, Costa P, et al. Involuntary movements after correction of vitamin B12 deficiency: A video-case report. Epileptic Disord 2012;14(2):174-80. PubMed
- Fanidi A, Carreras-Torres R, Larose TL, et al. Is high vitamin B12 status a cause of lung cancer? Int J Cancer. 2019 Sep 15;145(6):1499-1503. PubMed
- Fujita Y, Mizukami T, Maya Y, et al. Vitamin B12 allergy manifesting as lymphomatoid contact dermatitis. Eur J Dermatol. 2020;30(3):304-305. PubMed
- Dépret F, Hoffmann C, Daoud L, et al. Association between hydroxocobalamin administration and acute kidney injury after smoke inhalation: a multicenter retrospective study. Crit Care. 2019;23(1):421. PubMed
- Khairan P, Sobue T, Eshak ES, et al. Association of dietary intakes of vitamin B12, vitamin B6, folate, and methionine with the risk of esophageal cancer: the Japan Public Health Center-based (JPHC) prospective study. BMC Cancer 2021;21(1):982. PubMed
- Evans J, Pandya A, Ding Y, Qunibi WY. Hydroxocobalamin-Induced Oxalate Nephropathy in a Patient With Smoke Inhalation. Kidney Int Rep 2021;6(8):2228-2231. PubMed
- Lacombe V, Chabrun F, Lacout C, et al. Persistent elevation of plasma vitamin B12 is strongly associated with solid cancer. Sci Rep 2021;11(1):13361. PubMed
- Pegalajar-García MD, Cebolla-Verdugo M, Prados-Carmona Á, Llamas-Segura C, Navarro-Triviño FJ. Systemic allergic dermatitis to cobalt present in cyanocobalamin supplementation. Contact Dermatitis 2023;89(3):203-205. PubMed
L-arginine 66 references
- Sapienza MA, Kharitonov SA, Horvath I, et al. Effect of inhaled L-arginine on exhaled nitric oxide in normal and asthmatic subjects. Thorax 1998;53:172-5.
- Clarkson P, Adams MR, Powe AJ, et al. Oral L-arginine improves endothelium-dependent dilation in hypercholesterolemic young adults. J Clin Invest 1996;97:1989-94. PubMed
- Tenenbaum A, Fisman EZ, Motro M. L-arginine: Rediscovery in progress. Cardiology 1998;90:153-9.
- Brittenden J, Park KGM, Heys SD, et al. L-Arginine stimulates host defenses in patients with breast cancer. Surgery 1994;115:205-12.
- Korting GE, Smith SD, Wheeler MA, et al. A randomized double-blind trial of oral L-arginine for treatment of interstitial cystitis. J Urol 1999;161:558-65. DOI
- Rector TS, Bank AJ, Mullen KA, et al. Randomized, double-blind, placebo-controlled study of supplemental oral L-arginine in patients with heart failure. Circulation 1996;93:2135-41.
- Siani A, Pagano E, Iacone R, et al. Blood pressure and metabolic changes during dietary L-arginine supplementation in humans. Am J Hypertens 2000;13:547-51. PubMed
- Cheng JW, Balwin SN. L-arginine in the management of cardiovascular diseases. Ann Pharmacother 2001;35:755-64. PubMed
- Wallace AW, Tom WL. Interaction of L-arginine and phosphodiesterase inhibitors in vasodilation of the porcine internal mammary artery. Anesth Analg 2000;90:840-6. DOI
- Huynh NT, Tayek JA. Oral arginine reduces systemic blood pressure in type 2 diabetes: its potential role in nitric oxide generation. J Am Coll Nutr 2002;21:422-7.. PubMed
- Staff AC, Berge L, Haugen G, et al. Dietary supplementation with L-arginine or placebo in women with pre-eclampsia. Acta Obstet Gynecol Scand 2004;83:103-7.
- Resnick DJ, Softness B, Murphy AR, et al. Case report of an anaphylactoid reaction to arginine. Ann Allergy Asthma Immunol 2002;88:67-8. PubMed
- Anon. Arginine hydrochloride injection (marketed as R-Gene 10). FDA Drug Safety Newsletter 2009;2(2):16-18. Available at: www.fda.gov/Drugs/DrugSafety/DrugSafetyNewsletter/default.htm.
- Higashi Y, Oshima T, Sasaki S, et. al. Angiotensin-converting enzyme inhibition, but not calcium antagonism, improves a response of the renal vasculature to L-arginine in patients with essential hypertension. Hypertension. 1998 Jul;32(1):16-24.
- Facchinetti, F., Longo, M., Piccinini, F., Neri, I., and Volpe, A. L-arginine infusion reduces blood pressure in preeclamptic women through nitric oxide release. J Soc Gynecol.Investig. 1999;6(4):202-207. DOI
- de Gouw, H. W., Verbruggen, M. B., Twiss, I. M., and Sterk, P. J. Effect of oral L-arginine on airway hyperresponsiveness to histamine in asthma. Thorax 1999;54(11):1033-1035. PubMed
- Komers, R., Komersova, K., Kazdova, L., Ruzickova, J., and Pelikanova, T. Effect of ACE inhibition and angiotensin AT1 receptor blockade on renal and blood pressure response to L-arginine in humans. J Hypertens. 2000;18(1):51-59. PubMed
- Cartledge, J. J., Davies, A. M., and Eardley, I. A randomized double-blind placebo-controlled crossover trial of the efficacy of L-arginine in the treatment of interstitial cystitis. BJU.Int. 2000;85(4):421-426.
- Sozykin, A. V., Noeva, E. A., Balakhonova, T. V., Pogorelova, O. A., and Men'shikov, M. I. [Effect of L-arginine on platelet aggregation, endothelial function adn exercise tolerance in patients with stable angina pectoris]. Ter.Arkh. 2000;72(8):24-27.
- Nagaya, N., Uematsu, M., Oya, H., Sato, N., Sakamaki, F., Kyotani, S., Ueno, K., Nakanishi, N., Yamagishi, M., and Miyatake, K. Short-term oral administration of L-arginine improves hemodynamics and exercise capacity in patients with precapillary pulmona
- Stokes, G. S., Barin, E. S., Gilfillan, K. L., and Kaesemeyer, W. H. Interactions of L-arginine, isosorbide mononitrate, and angiotensin II inhibitors on arterial pulse wave. Am J Hypertens. 2003;16(9 Pt 1):719-724.
- Park, K. G., Heys, S. D., Blessing, K., Kelly, P., McNurlan, M. A., Eremin, O., and Garlick, P. J. Stimulation of human breast cancers by dietary L-arginine. Clin.Sci.(Lond) 1992;82(4):413-417.
- Palloshi, A., Fragasso, G., Piatti, P., Monti, L. D., Setola, E., Valsecchi, G., Galluccio, E., Chierchia, S. L., and Margonato, A. Effect of oral L-arginine on blood pressure and symptoms and endothelial function in patients with systemic hypertension,
- Schlaich, M. P., Ahlers, B. A., Parnell, M. M., and Kaye, D. M. beta-Adrenoceptor-mediated, nitric-oxide-dependent vasodilatation is abnormal in early hypertension: restoration by L-arginine. J Hypertens. 2004;22(10):1917-1925. PubMed
- Neri, I., Blasi, I., and Facchinetti, F. Effects of acute L-arginine infusion on non-stress test in hypertensive pregnant women. J Matern.Fetal Neonatal Med. 2004;16(1):23-26. PubMed
- Rytlewski, K., Olszanecki, R., Korbut, R., and Zdebski, Z. Effects of prolonged oral supplementation with l-arginine on blood pressure and nitric oxide synthesis in preeclampsia. Eur.J Clin.Invest 2005;35(1):32-37.
- Mansoor, J. K., Morrissey, B. M., Walby, W. F., Yoneda, K. Y., Juarez, M., Kajekar, R., Severinghaus, J. W., Eldridge, M. W., and Schelegle, E. S. L-arginine supplementation enhances exhaled NO, breath condensate VEGF, and headache at 4,342 m. High Alt.M
- Neri, I., Jasonni, V. M., Gori, G. F., Blasi, I., and Facchinetti, F. Effect of L-arginine on blood pressure in pregnancy-induced hypertension: a randomized placebo-controlled trial. J Matern.Fetal Neonatal Med. 2006;19(5):277-281.
- Lucotti, P., Setola, E., Monti, L. D., Galluccio, E., Costa, S., Sandoli, E. P., Fermo, I., Rabaiotti, G., Gatti, R., and Piatti, P. Beneficial effects of a long-term oral L-arginine treatment added to a hypocaloric diet and exercise training program in
- Savoye, G., Jemaa, Y., Mosni, G., Savoye-Collet, C., Morcamp, P., Dechelotte, P., Bouin, M., Denis, P., and Ducrotte, P. Effects of intragastric L-arginine administration on proximal stomach tone under basal conditions and after an intragastric diet. Dig PubMed
- Facchinetti, F., Saade, G. R., Neri, I., Pizzi, C., Longo, M., and Volpe, A. L-arginine supplementation in patients with gestational hypertension: a pilot study. Hypertens.Pregnancy. 2007;26(1):121-130. PubMed
- Jovanovic, A., Gerrard, J., and Taylor, R. The second-meal phenomenon in type 2 diabetes. Diabetes Care 2009;32(7):1199-1201. PubMed
- Fontanive P, Saponati G, Iurato A, et al. Effects of L-arginine on the Minnesota Living with Heart Failure Questionnaire quality-of-life score in patients with chronic systolic heart failure. Med.Sci.Monit. 2009;15:CR606-11.
- Doutreleau, S., Rouyer, O., Di, Marco P., Lonsdorfer, E., Richard, R., Piquard, F., and Geny, B. L-arginine supplementation improves exercise capacity after a heart transplant. Am J Clin.Nutr. 2010;91(5):1261-1267. PubMed
- Ast, J., Jablecka, A., Bogdanski, P., Smolarek, I., Krauss, H., and Chmara, E. Evaluation of the antihypertensive effect of L-arginine supplementation in patients with mild hypertension assessed with ambulatory blood pressure monitoring. Med.Sci.Monit. 2
- Saleh, A. I., Abdel Maksoud, S. M., El-Maraghy, S. A., and Gad, M. Z. Protective effect of L-arginine in experimentally induced myocardial ischemia: comparison with aspirin. J Cardiovasc.Pharmacol.Ther 2011;16(1):53-62. PubMed
- Dong, J. Y., Qin, L. Q., Zhang, Z., Zhao, Y., Wang, J., Arigoni, F., and Zhang, W. Effect of oral L-arginine supplementation on blood pressure: a meta-analysis of randomized, double-blind, placebo-controlled trials. Am.Heart J 2011;162(6):959-965. PubMed
- Hertz, P. and Richardson, J. A. Arginine-induced hyperkalemia in renal failure patients. Arch.Intern.Med. 1972;130(5):778-780. DOI
- Bushinsky, D. A. and Gennari, F. J. Life-threatening hyperkalemia induced by arginine. Ann.Intern.Med. 1978;89(5 Pt 1):632-634. PubMed
- Adams, M. R., Forsyth, C. J., Jessup, W., Robinson, J., and Celermajer, D. S. Oral L-arginine inhibits platelet aggregation but does not enhance endothelium-dependent dilation in healthy young men. J Am Coll.Cardiol 1995;26(4):1054-1061. PubMed
- Dell'Omo, G., Catapano, G., Ebel, M., Gazzano, A., Ducci, M., Del, Chicca M., Clerico, A., and Pedrinelli, R. [Pressor, renal and endocrine effects of systemic infusion of L-arginine in hypertensive patients]. Ann.Ital Med.Int. 1995;10(2):107-112.
- Higashi, Y., Oshima, T., Ozono, R., Watanabe, M., Matsuura, H., and Kajiyama, G. Effects of L-arginine infusion on renal hemodynamics in patients with mild essential hypertension. Hypertension 1995;25(4 Pt 2):898-902.
- Bode-Boger, S. M., Boger, R. H., Creutzig, A., Tsikas, D., Gutzki, F. M., Alexander, K., and Frolich, J. C. L-arginine infusion decreases peripheral arterial resistance and inhibits platelet aggregation in healthy subjects. Clin.Sci.(Lond) 1994;87(3):303
- Marfella, R., Acampora, R., Verrazzo, G., Ziccardi, P., De, Rosa N., Giunta, R., and Giugliano, D. Metformin improves hemodynamic and rheological responses to L-arginine in NIDDM patients. Diabetes Care 1996;19(9):934-939. PubMed
- Giugliano, D., Marfella, R., Verrazzo, G., Acampora, R., Coppola, L., Cozzolino, D., and D'Onofrio, F. The vascular effects of L-Arginine in humans. The role of endogenous insulin. J Clin.Invest 2-1-1997;99(3):433-438. PubMed
- Khan, F., Litchfield, S. J., McLaren, M., Veale, D. J., Littleford, R. C., and Belch, J. J. Oral L-arginine supplementation and cutaneous vascular responses in patients with primary Raynaud's phenomenon. Arthritis Rheum. 1997;40(2):352-357.
- Wolf, A., Zalpour, C., Theilmeier, G., Wang, B. Y., Ma, A., Anderson, B., Tsao, P. S., and Cooke, J. P. Dietary L-arginine supplementation normalizes platelet aggregation in hypercholesterolemic humans. J Am Coll.Cardiol 3-1-1997;29(3):479-485. PubMed
- Schellong, S. M., Boger, R. H., Burchert, W., Bode-Boger, S. M., Galland, A., Frolich, J. C., Hundeshagen, H., and Alexander, K. Dose-related effect of intravenous L-arginine on muscular blood flow of the calf in patients with peripheral vascular disease
- Marietta, M., Facchinetti, F., Neri, I., Piccinini, F., Volpe, A., and Torelli, G. L-arginine infusion decreases platelet aggregation through an intraplatelet nitric oxide release. Thromb.Res 10-15-1997;88(2):229-235. PubMed
- Bauer JD, Isenring E, Waterhouse M. The effectiveness of a specialised oral nutrition supplement on outcomes in patients with chronic wounds: a pragmatic randomised study. J Hum Nutr Diet. 2013 Oct;26(5):452-8. PubMed
- Vadillo-Ortega F, Perichart-Perera O, Espino S, et al. Effect of supplementation during pregnancy with L-arginine and antioxidant vitamins in medical food on pre-eclampsia in high risk population: randomised controlled trial. BMJ. 2011 May 19;342:d2901. PubMed
- Camarena Pulido EE, García Benavides L, Panduro Barón JG, et al. Efficacy of L-arginine for preventing preeclampsia in high-risk pregnancies: A double-blind, randomized, clinical trial. Hypertens Pregnancy. 2016;35(2):217-25. PubMed
- Yokota T, Hamauchi S, Yoshida Y, et al. A phase II study of HMB/Arg/Gln against oral mucositis induced by chemoradiotherapy for patients with head and neck cancer. Support Care Cancer. 2018;26(9):3241-3248. PubMed
- Binet Q, Dufour I, Agneessens E, et al. The second case of a young man with L-arginine-induced acute pancreatitis. Clin J Gastroenterol. 2018;11(5):424-427. PubMed
- El Taieb M, Hegazy E, Ibrahim A. Daily oral l-arginine plus tadalafil in diabetic patients with erectile dysfunction: A double-blinded, randomized, controlled clinical trial. J Sex Med. 2019;16(9):1390-1397.
- Gallo L, Pecoraro S, Sarnacchiaro P, Silvani M, Antonini G. The daily therapy with L-arginine 2,500 mg and tadalafil 5 mg in combination and in monotherapy for the treatment of erectile dysfunction: A prospective, randomized multicentre study. Sex Med. 20 PubMed
- de la Parra PR, González-Cruz MÁ, Ferreiro-Marin A, Casaubón-Garcín PR. L-arginine-induced esophagitis, report of six cases. Bol Med Hosp Infant Mex. 2020;77(1):38-41. PubMed
- El-Wakeel LM, Fouad FA, Saleem MD, Saber-Khalaf M. Efficacy and tolerability of sildenafil/l-arginine combination relative to sildenafil alone in patients with organic erectile dysfunction. Andrology. 2020;8(1):143-147.
- Abu El-Hamd M, Hegazy EM. Comparison of the clinical efficacy of daily use of L-arginine, tadalafil and combined L-arginine with tadalafil in the treatment of elderly patients with erectile dysfunction. Andrologia. 2020;52(7):e13640. PubMed
- Liao SY, Showalter MR, Linderholm AL, et al. l-Arginine supplementation in severe asthma. JCI Insight. 2020;5(13):e137777. PubMed
- Yousefi Rad E, Nazarian B, Saboori S, Falahi E, Hekmatdoost A. Effects of l-arginine supplementation on glycemic profile: Evidence from a systematic review and meta-analysis of clinical trials. J Integr Med. 2020;18(4):284-291. PubMed
- Xu Z, Liu C, Liu S, Zhou Z. Comparison of efficacy and safety of daily oral L-arginine and PDE5Is alone or combination in treating erectile dysfunction: A systematic review and meta-analysis of randomised controlled trials. Andrologia. 2021:e14007. PubMed
- Goto E. Effects of prenatal oral L-arginine on birth outcomes: a meta-analysis. Sci Rep 2021;11(1):22748. PubMed
- Monari F, Menichini D, Pignatti L, Basile L, Facchinetti F, Neri I. Effect of L-arginine supplementation in pregnant women with chronic hypertension and previous placenta vascular disorders receiving Aspirin prophylaxis: a randomized control trial. Minerv PubMed
- Li H, Liu Q, Zou Z, et al. L-arginine supplementation to mitigate cardiovascular effects of walking outside in the context of traffic-related air pollution in participants with elevated blood pressure: A randomized, double-blind, placebo-controlled trial. PubMed
- Shiraseb F, Asbaghi O, Bagheri R, Wong A, Figueroa A, Mirzaei K. The Effect of L-arginine Supplementation On Blood Pressure in Adults: A Systematic Review and Dose-response Meta-analysis of Randomized Clinical Trials. Adv Nutr 2021. PubMed
Tyrosine 4 references
- Meyer JS, Welch KM, Deshmukh VD, et al. Neurotransmitter precursor amino acids in the treatment of multi-infarct dementia and Alzheimer's disease. J Amer Geriat Soc 1977;25:289-98.
- DiPiro JT, Talbert RL, Yee GC, et al; eds. Pharmacotherapy: A pathophysiologic approach. 4th ed. Stamford, CT: Appleton & Lange, 1999.
- Wood DR, Reimherr FW, Wender PH. Amino acid precursors for the treatment of attention deficit disorder, residual type. Psychopharmacol Bull 1985;21:146-9.
- van Spronsen FJ, van Rijn M, Bekhof J. Phenylketonuria: tyrosine supplementation in phenylalanine-restricted diets. Am J Clin Nutr 2001;73:153-7. PubMed
Zinc 88 references
- Barceloux DG. Zinc. J Toxicol Clin Toxicol 1999;37:279-92.
- Eby GA, Davis DR, Halcomb WW. Reduction in duration of common colds by zinc gluconate lozenges in a double-blind study. Antimicrob Agents Chemother 1984;25:20-4. DOI
- Smith DS, Helzner EC, Nuttall CE Jr, et al. Failure of zinc gluconate in treatment of acute upper respiratory tract infections. Antimicrob Agents Chemother 1989;33:646-8. PubMed
- Blondeau JM. Expanded activity and utility of the new fluoroquinolones: a review. Clin Ther 1999;21:3-40. PubMed
- Reyes AJ, Olhaberry JV, Leary WP, et al. Urinary zinc excretion, diuretics, zinc deficiency and some side-effects of diuretics. S Afr Med J 1983;64:936-41.
- Kugelmas M. Preliminary observation: oral zinc sulfate replacement is effective in treating muscle cramps in cirrhotic patients. J Am Coll Nutr 2000;19:13-5. PubMed
- Hebel SK, ed. Drug Facts and Comparisons. 52nd ed. St. Louis: Facts and Comparisons, 1998.
- Chan S, Gerson B, Subramaniam S. The role of copper, molybdenum, selenium, and zinc in nutrition and health. Clin Lab Med 1998;18:673-85. DOI
- Brewer GJ, Yuzbasiyan-Gurkan V, Johnson V, et al. Treatment of Wilson's disease with zinc: XI. Interaction with other anticopper agents. J Am Coll Nutr 1993;12:26-30. PubMed
- Fosmire GJ. Zinc toxicity. Am J Clin Nutr 1990;51:225-7.
- Lomaestro BM, Bailie GR. Absorption interactions with fluoroquinolones. 1995 update. Drug Saf 1995;12:314-33. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Seelig MS. Auto-immune complications of D-penicillamine - A possible result of zinc and magnesium depletion and of pyridoxine inactivation. J Am Coll Nutr 1982;1:207-14. PubMed
- Neuvonen PJ. Interactions with the absorption of tetracyclines. Drugs 1976;11:45-54.. PubMed
- Hirt M, Nobel S, Barron E. Zinc nasal gel for the treatment of common cold symptoms: A double-blind, placebo-controlled trial. Ear Nose Throat J 2000;79:778-82.. DOI
- Simkin PA. Oral zinc sulphate in rheumatoid arthritis. Lancet 1976;2:539-42. PubMed
- Wray D. A double-blind trial of systemic zinc sulfate in recurrent aphthous stomatitis. Oral Surg Oral Med Oral Pathol 1982;53:469-72. PubMed
- Douglas RM, Miles HB, Moore BW, et al. Failure of effervescent zinc acetate lozenges to alter the course of upper respiratory tract infections in Australian adults. Antimicrob Agents Chemother 1987;31:1263-5. PubMed
- Lagiou P, Wuu J, Trichopoulou A, et al. Diet and benign prostatic hyperplasia: a study in Greece. Urology 1999;54:284-90. PubMed
- Ewing CI, Gibbs AC, Ashcroft C, David TJ. Failure of oral zinc supplementation in atopic eczema. Eur J Clin Nutr 1991;45:507-10.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Age-Related Eye Disease Study Research Group. A randomized, placebo-controlled, clinical trial of high-dose supplementation with vitamins C and E, beta carotene, and zinc for age-related macular degeneration and vision loss. AREDS report no. 8. Arch Oph
- Greenberg JE, Lynn M, Kirsner RS, et al. Mucocutaneous pigmented macule as a result of zinc deposition. J Cutan Pathol 2002;29:613-5. PubMed
- Godfrey HR, Godfrey NJ, Godfrey JC, Riley D. A randomized clinical trial on the treatment of oral herpes with topical zinc oxide/glycine. Altern Ther Health Med 2001;7:49-56.
- Turner RB. Ineffectiveness of intranasal zinc gluconate for prevention of experimental rhinovirus colds. Clin Infect Dis 2001;33:1865-70. PubMed
- Belongia EA, Berg R, Liu K. A randomized trial of zinc nasal spray for the treatment of upper respiratory illness in adults. Am J Med 2001;111:103-8. PubMed
- Mossad SB. Effect of zincum gluconicum nasal gel on the duration and symptom severity of the common cold in otherwise healthy adults. QJM 2003;96:35-43. DOI
- Leitzmann MF, Stampfer MJ, Wu K, et al. Zinc supplement use and risk of prostate cancer. J Natl Cancer Inst 2003;95:1004-7.. PubMed
- Jafek BW, Linschoten M, Murrow BW. Zicam Induced Anosmia. American Rhinologic Society 49th Annual Fall Scientific Meeting abstract. Orlando, Florida. September 20, 2003. http://app.american-rhinologic.org/programs/2003ARSFallProgram071503.pdf (Accessed 24
- Uebayashi H, Hatanaka T, Kanemura F, Tonosaki K. Acute anosmia in the mouse: behavioral discrimination among the four basic taste substances. Physiol Behav 2001;72:291-6.. PubMed
- Barrett S. Zicam Marketers Sued. United States District Court Western District of Michigan Southern Division, Filed October 14, 2003, Case No. 4:03CV0146.
- Bilici M, Yildirim F, Kandil S, et al. Double-blind, placebo-controlled study of zinc sulfate in the treatment of attention deficit hyperactivity disorder. Prog Neuropsychopharmacol Biol Psychiatry 2004;28:181-90.. PubMed
- Polk RE, Healy DP, Sahai J, et al. Effect of ferrous sulfate and multivitamins with zinc on absorption of ciprofloxacin in normal volunteers. Antimicrob Agents Chemother 1989;33:1841-4. PubMed
- Mery C, Delrieu F, Ghozlan R, et al. Controlled trial of D-penicillamine in rheumatoid arthritis. Dose effect and the role of zinc. Scand J Rheumatol 1976;5:241-7. PubMed
- Penttila O, Hurme H, Neuvonen PJ. Effect of zinc sulfate on the absorption of tetracycline and doxycycline in man. Eur J Clin Pharmacol 1975;9:131-4.
- Kondo Y, Yamagata K, Satoh M, et al. Optimal administration schedule of cisplatin for bladder tumor with minimal induction of metallothionein. J Urol 2003;170:2467-70. PubMed
- Doz F, Berens ME, Deschepper CF, et al. Experimental basis for increasing the therapeutic index of cis-diamminedicarboxylatocyclobutaneplatinum(II) in brain tumor therapy by a high-zinc diet. Cancer Chemother Pharmacol 1992;29:219-26.
- Wester PO. Urinary zinc excretion during treatment with different diuretics. Acta Med Scand 1980;208:209-12. PubMed
- Golik A, Modai D, Weissgarten J, et al. Hydrochlorothiazide-amiloride causes excessive urinary zinc excretion. Clin Pharmacol Ther 1987;42:42-4. PubMed
- Leary WP, Reyes AJ, Van der Byl K. Urinary magnesium and zinc excretion after two different single doses of amiloride in healthy adults. Curr Ther Res 1983;34:205-16.
- McBride K, Slotnick B, Margolis FL. Does intranasal application of zinc sulfate produce anosmia in the mouse? An olfactometric and anatomical study. Chem Senses 2003;28:659-70. PubMed
- Burd GD. Morphological study of the effects of intranasal zinc sulfate irrigation on the mouse olfactory epithelium and olfactory bulb. Microsc Res Tech 1993;24:195-213. PubMed
- Ducray A, Bondier JR, Michel G, et al. Recovery following peripheral destruction of olfactory neurons in young and adult mice. Eur J Neurosci 2002;15:1907-17. PubMed
- Mayer AD, Rosenblatt JS. Peripheral olfactory deafferentation of the primary olfactory system in rats using ZnSO4 nasal spray with special reference to maternal behavior. Physiol Behav 1993;53:587-92. PubMed
- DeCook CA, Hirsch AR. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Tisdall FF, Brown A, Defries RD. Persistent anosmia following zinc sulfate nasal spraying. JPed 1938;18:60-2. DOI
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Public Health Advisory. Loss of sense of smell with intranasal cold remedies containing zinc. U.S. Food and Drug Administration, June 16, 2009. Available at: http://www.fda.gov/Drugs/DrugSafety/PublicHealthAdvisories/ucm166059.htm (Accessed 16 June 2009)
- Dooren JC. FDA warns against use of Zicam. The Wall Street Journal, June 16, 2009. Available at: http://online.wsj.com/article/SB124516778692319231.html#mod=djemHL?mg=com-wsj (Accessed 16 June 2009).
- Alexander TH, Davidson TM. Intranasal zinc and anosmia: the zinc-induced anosmia syndrome. Laryngoscope 2006;116:217-20.
- Health Canada / GlaxoSmithKline Consumer Healthcare. Association of long-term, excessive use of zinc-containing Poli-Grip products with myeloneuropathy and blood dyscrasias. February 18, 2010. Available at: http://hc-sc.gc.ca/dhp-mps/alt_formats/pdf/medef
- GlaxoSmithKline Consumer Advisory. GlaxoSmithKline (GSK) warns about a potential health risk associated with long-term, excessive use of GSK's zinc-containing denture adhesives Super Polygrip Original, Ultra Fresh and Extra Care. February 18, 2010. Availa
- Science M, Johnstone J, Roth DE, et al. Zinc for the treatment of the common cold: a systematic review and meta-analysis of randomized controlled trials. CMAJ 2012;184:E551-61. PubMed
- Castilla-Higuero, L., Romero-Gomez, M., Suarez, E., and Castro, M. Acute hepatitis after starting zinc therapy in a patient with presymptomatic Wilson's disease. Hepatology 2000;32(4 Pt 1):877. PubMed
- Sharquie, K. E., Najim, R. A., Farjou, I. B., and Al Timimi, D. J. Oral zinc sulphate in the treatment of acute cutaneous leishmaniasis. Clin.Exp.Dermatol. 2001;26(1):21-26. PubMed
- Dreno, B., Moyse, D., Alirezai, M., Amblard, P., Auffret, N., Beylot, C., Bodokh, I., Chivot, M., Daniel, F., Humbert, P., Meynadier, J., and Poli, F. Multicenter randomized comparative double-blind controlled clinical trial of the safety and efficacy of
- Moore, R. Bleeding gastric erosion after oral zinc sulphate. Br.Med J 3-25-1978;1(6115):754. PubMed
- Jafek, B. W., Linschoten, M. R., and Murrow, B. W. Anosmia after intranasal zinc gluconate use. Am J Rhinol. 2004;18(3):137-141. DOI
- Simonart, T. and de, Maertelaer, V. Systemic treatments for cutaneous warts: a systematic review. J Dermatolog.Treat. 2012;23(1):72-77. PubMed
- Cochran, R. J., Tucker, S. B., and Flannigan, S. A. Topical zinc therapy for acne vulgaris. Int.J Dermatol. 1985;24(3):188-190. DOI
- Morgan, A. A. Bleeding gastric erosion after oral zinc sulphate. Br.Med.J. 5-13-1978;1(6122):1283-1284. PubMed
- Murphy, J. V. Intoxication following ingestion of elemental zinc. JAMA 6-22-1970;212(12):2119-2120.
- Lang, C. J., Rabas-Kolominsky, P., Engelhardt, A., Kobras, G., and Konig, H. J. Fatal deterioration of Wilson's disease after institution of oral zinc therapy. Arch Neurol. 1993;50(10):1007-1008. PubMed
- Fjellner, B. Drug-induced lupus erythematosus aggravated by oral zinc therapy. Acta Derm.Venereol. 1979;59(4):368-370. DOI
- Varas Lorenzo, M. J. Zinc acexamate and ranitidine in the short- and mid-term management of gastroduodenal ulcers. Curr Ther Res 21986;39:19-29.
- Bosch, F. and Jimenez, E. Post-marketing surveillance of zinc acexamate in peptic ulcer treatment. Clin Trials J 1990;27:301-312.
- DeCook, C. A. and Hirsch, A. R. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Crown LA, May JA. Zinc toxicity: denture adhesives, bone marrow failure and polyneuropathy. Tenn Med. 2012 Feb;105(2):39-40, 42.
- Dadamio J, Van Tournout M, Teughels W, Dekeyser C, Coucke W, Quirynen M. Efficacy of different mouthrinse formulations in reducing oral malodour: a randomized clinical trial. J Clin Periodontol. 2013 May;40(5):505-13. PubMed
- Moyle G, Else L, Jackson A, Back D, Yapa MH, Seymour N, Ringner-Nackter L, Karolia Z, Gazzard B, Boffito M. Coadministration of atazanavir-ritonavir and zinc sulfate: impact on hyperbilirubinemia and pharmacokinetics. Antimicrob Agents Chemother. 2013 Aug PubMed
- Zittel S, Ufer F, Gerloff C, Münchau A, Rosenkranz M. Severe myelopathy after denture cream use--is copper deficiency or excess zinc the cause? Clin Neurol Neurosurg. 2014 Jun;121:17-8. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Guidelines for the Use of Antiretroviral Agents in HIV-1-Infected Adults and Adolescents: Drug Interactions between Integrase Inhibitors and Other Drugs. AIDSinfo. July 14, 2016. Available at: https://aidsinfo.nih.gov/guidelines/html/1/adult-and-adolescen
- Ding Y, Jia YY, Li F, et al. The effect of staggered administration of zinc sulfate on the pharmacokinetics of oral cephalexin. Br J Clin Pharmacol. 2012 Mar;73(3):422-7. PubMed
- Fallah R, Sabbaghzadegan S, Karbasi SA, Binesh F. Efficacy of zinc sulfate supplement on febrile seizure recurrence prevention in children with normal serum zinc level: A randomised clinical trial. Nutrition. 2015;31(11-12):1358-61. PubMed
- Lazzerini M, Wanzira H. Oral zinc for treating diarrhoea in children. Cochrane Database Syst Rev. 2016;12:CD005436. PubMed
- Mahmoud AM, Al-Alem U, Dabbous F, et al. Zinc intake and risk of prostate cancer: Case-control study and meta-analysis. PLoS One. 2016;11(11):e0165956. PubMed
- Nagraj SK, George RP, Shetty N, Levenson D, Ferraiolo DM, Shrestha A. Interventions for managing taste disturbances. Cochrane Database Syst Rev. 2017 Dec 20;12(12):CD010470. PubMed
- Yee BE, Richards P, Sui JY, Marsch AF. Serum zinc levels and efficacy of zinc treatment in acne vulgaris: A systematic review and meta-analysis. Dermatol Ther. 2020:e14252. PubMed
- Janyajirawong R, Vilaichone RK, Sethasine S. Efficacy of zinc supplement in minimal hepatic encephalopathy: A prospective, randomized controlled study (Zinc-MHE Trial). Asian Pac J Cancer Prev 2021;22(9):2879-2887. PubMed
- Nakano M, Nakamura Y, Miyazaki A, Takahashi J. Zinc pharmacotherapy for elderly osteoporotic patients with zinc deficiency in a clinical setting. Nutrients 2021;13(6):1814. PubMed
- Tolino E, Skroza N, Mambrin A, et al. An open-label study comparing oral zinc to lymecycline in the treatment of acne vulgaris. J Clin Aesthet Dermatol 2021;14(5):56-58.
- Hunter J, Arentz S, Goldenberg J, et al. Zinc for the prevention or treatment of acute viral respiratory tract infections in adults: a rapid systematic review and meta-analysis of randomised controlled trials. BMJ Open. 2021;11(11):e047474. PubMed
- Yamazaki K, Kageyama H, Fujiyama T, Ito T, Urano S, Honda T. A case of systemic contact dermatitis due to zinc supplements. Int J Dermatol 2022. PubMed
- Magham K, Han J, Eilbert W, Bunney EB. Severe copper deficiency anemia caused by zinc supplement use. Am J Emerg Med 2023;72:222. PubMed
- Sivakumar RR, Chinnaiah Govindareddy D, Sahoo J, Bobby Z, Chinnakali P. Effect of daily zinc supplementation for 12 weeks on serum thyroid auto-antibody levels in children and adolescents with autoimmune thyroiditis - a randomized controlled trial. J Pedi PubMed
- AlDhasee O, AlMalki H, AlKharashi N, AlJeraisy N, Al Deeb M. Acute zinc sulfate overdose: clinical presentation and management. BMJ Case Rep 2025;18(1):e263899. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Black Pepper 29 references
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
- Bano G, Amla V, Raina RK, et al. The effect of piperine on pharmacokinetics of phenytoin in healthy volunteers. Planta Med 1987;53:568-9. PubMed
- Bano G, et al. Effect of piperine on bioavailability and pharmacokinetics of propranolol and theophylline in healthy volunteers. Eur J Clin Pharmacol 1991;41;615-7. PubMed
- Cohle SD, Trestrail JD III, Graham MA, et al. Fatal pepper aspiration. Am J Dis Child 1988;142:633-6. PubMed
- Bhardwaj RK, Glaeser H, Becquemont L, et al. Piperine, a major constituent of black pepper, inhibits human P-glycoprotein and CYP3A4. J Pharmacol Exp Ther 2002;302:645-50. PubMed
- Velpandian T, Jasuja R, Bhardwaj RK, et al. Piperine in food: interference in the pharmacokinetics of phenytoin. Eur J Drug Metab Pharmacokinet 2001;26:241-7. PubMed
- Pattanaik S, Hota D, Prabhakar S, et al. Pharmacokinetic interaction of a single dose of piperine with steady-state carbamazepine in epilepsy patients. Phytother Res 2009;23:1281-6.
- Munakata, M., Kobayashi, K., Niisato-Nezu, J., Tanaka, S., Kakisaka, Y., Ebihara, T., Ebihara, S., Haginoya, K., Tsuchiya, S., and Onuma, A. Olfactory stimulation using black pepper oil facilitates oral feeding in pediatric patients receiving long-term en
- Myers, B. M., Smith, J. L., and Graham, D. Y. Effect of red pepper and black pepper on the stomach. Am J Gastroenterol 1987;82(3):211-214.
- Raghavendra, R. H. and Naidu, K. A. Spice active principles as the inhibitors of human platelet aggregation and thromboxane biosynthesis. Prostaglandins Leukot.Essent.Fatty Acids 2009;81(1):73-78. PubMed
- Subehan, Usia, T., Kadota, S., and Tezuka, Y. Mechanism-based inhibition of human liver microsomal cytochrome P450 2D6 (CYP2D6) by alkamides of Piper nigrum. Planta Med 2006;72(6):527-532.
- Kasibhatta, R. and Naidu, M. U. Influence of piperine on the pharmacokinetics of nevirapine under fasting conditions: a randomised, crossover, placebo-controlled study. Drugs R.D. 2007;8(6):383-391. PubMed
- Usia, T., Iwata, H., Hiratsuka, A., Watabe, T., Kadota, S., and Tezuka, Y. CYP3A4 and CYP2D6 inhibitory activities of Indonesian medicinal plants. Phytomedicine. 2006;13(1-2):67-73. PubMed
- Mujumdar, A. M., Dhuley, J. N., Deshmukh, V. K., Raman, P. H., Thorat, S. L., and Naik, S. R. Effect of piperine on pentobarbitone induced hypnosis in rats. Indian J Exp.Biol. 1990;28(5):486-487.
- Panda, S. and Kar, A. Piperine lowers the serum concentrations of thyroid hormones, glucose and hepatic 5'D activity in adult male mice. Horm.Metab Res. 2003;35(9):523-526. PubMed
- Lawless, H. and Stevens, D. A. Effects of oral chemical irritation on taste. Physiol Behav. 1984;32(6):995-998. PubMed
- Hiwale, A. R., Dhuley, J. N., and Naik, S. R. Effect of co-administration of piperine on pharmacokinetics of beta-lactam antibiotics in rats. Indian J Exp.Biol. 2002;40(3):277-281.
- Han, Y., Chin Tan, T. M., and Lim, L. Y. In vitro and in vivo evaluation of the effects of piperine on P-gp function and expression. Toxicol.Appl.Pharmacol. 8-1-2008;230(3):283-289. PubMed
- Sharma, P., Varma, M. V., Chawla, H. P., and Panchagnula, R. In situ and in vivo efficacy of peroral absorption enhancers in rats and correlation to in vitro mechanistic studies. Farmaco 2005;60(11-12):874-883. PubMed
- Aher, S., Biradar, S., Gopu, C. L., and Paradkar, A. Novel pepper extract for enhanced P-glycoprotein inhibition. J Pharm.Pharmacol. 2009;61(9):1179-1186. PubMed
- Zutshi, R. K., Singh, R., Zutshi, U., Johri, R. K., and Atal, C. K. Influence of piperine on rifampicin blood levels in patients of pulmonary tuberculosis. J Assoc.Physicians India 1985;33(3):223-224.
- Marotta, R. B. and Floch, M. H. Diet and nutrition in ulcer disease. Med Clin North Am 1991;75(4):967-979. PubMed
- Subehan, Usia, T., Iwata, H., Kadota, S., and Tezuka, Y. Mechanism-based inhibition of CYP3A4 and CYP2D6 by Indonesian medicinal plants. J Ethnopharmacol. 5-24-2006;105(3):449-455. PubMed
- Gimenez L, Zacharisen M. Severe pepper allergy in a young child. WMJ. 2011 Jun;110(3):138-9.
- Ren T, Yang M, Xiao M, Zhu J, Xie W, Zuo Z. Time-dependent inhibition of carbamazepine metabolism by piperine in anti-epileptic treatment. Life Sci. 2019;218:314-323. PubMed
- Thomas AB, Choudhary DC, Raje A, Nagrik SS. Pharmacokinetics and pharmacodynamic herb-drug interaction of piperine with atorvastatin in rats. J Chromatogr Sci 2021;59(4):371-80. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Lin F, Hu Y, Zhang Y, Zhao L, Zhong D, Liu J. Predicting Food-Drug Interactions between Piperine and CYP3A4 Substrate Drugs Using PBPK Modeling. Int J Mol Sci 2024;25(20):10955. PubMed
Niacin 66 references
- Garg R, Malinow MR, Pettinger M, et al. Niacin treatment increases plasma homocysteine levels. Am Heart J 1999;138:1082-7.
- Anon. Inositol hexaniacinate. Altern Med Rev 1998;3:222-3.
- Knodel LC, Talbert RL. Adverse effects of hypolipidaemic drugs. Med Toxicol 1987;2:10-32. PubMed
- Guyton JR, Blazing MA, Hagar J, et al. Extended-release niacin vs gemfibrozil for the treatment of low levels of high-density lipoprotein cholesterol. Niaspan-Gemfibrozil Study Group. Arch Intern Med 2000;160:1177-84. PubMed
- Gibbons LW, Gonzalez V, Gordon N, Grundy S. The prevalence of side effects with regular and sustained-release nicotinic acid. Am J Med 1995;99:378-85. PubMed
- Whelan AM, Price SO, Fowler SF, Hainer BL. The effect of aspirin on niacin-induced cutaneous reactions. J Fam Pract 1992;34:165-8.
- Jungnickel PW, Maloley PA, Vander Tuin EL, et al. Effect of two aspirin pretreatment regimens on niacin-induced cutaneous reactions. J Gen Intern Med 1997;12:591-6. PubMed
- Capuzzi DM, Guyton JR, Morgan JM, et al. Efficacy and safety of an extended-release niacin (Niaspan): a long-term study. Am J Cardiol 1998;82:74-81;disc. 85U-6U. PubMed
- Gray DR, Morgan T, Chretien SD, Kashyap ML. Efficacy and safety of controlled-release niacin in dyslipoproteinemic veterans. Ann Intern Med 1994;121:252-8. PubMed
- McKenney JM, Proctor JD, Harris S, Chinchili VM. A comparison of the efficacy and toxic effects of sustained- vs immediate-release niacin in hypercholesterolemic patients. JAMA 1994;271:672-7. DOI
- Knopp RH, Alagona P, Davidson M, et al. Equivalent efficacy of a time-release form of niacin (Niaspan) given once-a-night versus plain niacin in the management of hyperlipidemia. Metabolism 1998;47:1097-104. PubMed
- Knopp RH. Clinical profiles of plain versus sustained-release niacin (Niaspan) and the physiologic rationale for nighttime dosing. Am J Cardiol 1998;82:24U-28U;discussion 39U-41U. PubMed
- Garg A, Grundy SM. Nicotinic acid as therapy for dyslipidemia in non-insulin-dependent diabetes mellitus. JAMA 1990;264:723-6. DOI
- Leighton RF, Gordon NF, Small GS, et al. Dental and gingival pain as side effects of niacin therapy. Chest 1998;114:1472-4. PubMed
- American Society of Health-System Pharmacists. ASHP Therapeutic Position Statement on the safe use of niacin in the management of dyslipidemias. Am J Health Syst Pharm 1997;54:2815-9. DOI
- Vega GL, Grundy SM. Lipoprotein responses to treatment with lovastatin, gemfibrozil, and nicotinic acid in normolipidemic patients with hypoalphalipoproteinemia. Arch Intern Med 1994;154:73-82. DOI
- Guyton JR, Goldberg AC, Kreisberg RA, et al. Effectiveness of once-nightly dosing of extended-release niacin alone and in combination for hypercholesterolemia. Am J Cardiol 1998;82:737-43.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Bays HE, Dujovne CA. Drug interactions of lipid-altering drugs. Drug Saf 1998;19:355-71. PubMed
- Rader JI, Calvert RJ, Hathcock JN. Hepatic toxicity of unmodified and time-release preparations of niacin. Am J Med 1992;92:77-81. PubMed
- Kahn SE, Beard JC, Schwartz MW, et al. Increased B-cell secretory capacity as mechanism for islet adaptation to nicotinic acid-induced insulin resistance. Diabetes 1989;38:562-8.
- Schwartz ML. Severe reversible hyperglycemia as a consequence of niacin therapy. Arch Int Med 1993;153:2050-2. DOI
- Raising HDL and Niacin Use. Pharmacist's Letter/Prescriber's Letter 2004;20(5):200504.
- McKenney J. New perspectives on the use of niacin in the treatment of lipid disorders. Arch Intern Med 2004;164:697-705. PubMed
- Reaven P, Witztum JL. Lovastatin, nicotinic acid and rhabdomyolysis (letter). Ann Int Med 1988;109:597-8. PubMed
- Ito MK. Advances in the understanding and management of dyslipidemia: using niacin-based therapies. Am J Health-Syst Pharm 2003;60(suppl 2):s15-21. PubMed
- Schwab RA, Bachhuber BH. Delirium and lactic acidosis caused by ethanol and niacin coingestion. Am J Emerg Med 1991;9:363-5. PubMed
- Product information: Niaspan. Kos Pharmaceuticals. Cranbury, NJ. 2005. Available at www.niaspan.com/professional/content/pdfs/productinfo.pdf. (Accessed 3 March 2006).
- Ding RW, Kolbe K, Merz B, et al. Pharmacokinetics of nicotinic acid-salicylic acid interaction. Clin Pharmacol Ther 1989;46:642-7. PubMed
- NIH News. NIH stops clinical trial on combination cholesterol treatment. May 26, 2011. http://www.nih.gov/news/health/may2011/nhlbi-26.htm. (Accessed 3 June 2011).
- Dearing BD, Lavie CJ, Lohmann TP, Genton E. Niacin-induced clotting factor synthesis deficiency with coagulopathy. Arch Intern Med. 1992;152(4):861-3. DOI
- O'Brien T, Silverberg JD, Nguyen TT. Nicotinic acid-induced toxicity associated with cytopenia and decreased levels of thyroxine-binding globulin. Mayo Clin Proc. 1992;67(5):465-8. PubMed
- Gadegbeku CA, Dhandayuthapani A, Shrayyef MZ, Egan BM. Hemodynamic effects of nicotinic acid infusion in normotensive and hypertensive subjects. Am J Hypertens. 2003;16(1):67-71. PubMed
- Garnett WR. Interactions with hydroxymethylglutaryl-coenzyme A reductase inhibitors. Am J Health Syst Pharm. 1995;52(15):1639-45. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Dunn RT, Ford MA, Rindone JP, Kwiecinski FA. Low-Dose Aspirin and Ibuprofen Reduce the Cutaneous Reactions Following Niacin Administration. Am J Ther. 1995;2(7):478-480. PubMed
- Cashin-Hemphill L, Spencer CA, Nicoloff JT, et al. Alterations in serum thyroid hormonal indices with colestipol-niacin therapy. Ann Intern Med. 1987;107(3):324-9. PubMed
- Drinka PJ. Alterations in thyroid and hepatic function tests associated with preparations of sustained-release niacin. Mayo Clin Proc. 1992;67(12):1206. PubMed
- Shakir KM, Kroll S, Aprill BS, Drake AJ 3rd, Eisold JF. Nicotinic acid decreases serum thyroid hormone levels while maintaining a euthyroid state. Mayo Clin Proc. 1995;70(6):556-8. PubMed
- Etchason JA, Miller TD, Squires RW, et al. Niacin-induced hepatitis: a potential side effect with low-dose time-release niacin. Mayo Clin Proc. 1991;66(1):23-8. PubMed
- Henkin Y, Johnson KC, Segrest JP. Rechallenge with crystalline niacin after drug-induced hepatitis from sustained-release niacin. JAMA. 1990;264(2):241-3. DOI
- Henkin Y, Oberman A, Hurst DC, Segrest JP. Niacin revisited: clinical observations on an important but underutilized drug. Am J Med. 1991;91(3):239-46. PubMed
- Brown BG, Bardsley J, Poulin D, et al. Moderate dose, three-drug therapy with niacin, lovastatin, and colestipol to reduce low-density lipoprotein cholesterol <100 mg/dl in patients with hyperlipidemia and coronary artery disease. Am J Cardiol. 1997;80(2)
- Goldberg A, Alagona P Jr, Capuzzi DM, et al. Multiple-dose efficacy and safety of an extended-release form of niacin in the management of hyperlipidemia. Am J Cardiol. 2000;85(9):1100-5. PubMed
- Aronov DM, Keenan JM, Akhmedzhanov NM, et al. Clinical trial of wax-matrix sustained-release niacin in a Russian population with hypercholesterolemia. Arch Fam Med. 1996;5(10):567-75. PubMed
- Morgan JM, Capuzzi DM, Guyton JR, et al. Treatment Effect of Niaspan, a Controlled-release Niacin, in Patients With Hypercholesterolemia: A Placebo-controlled Trial. J Cardiovasc Pharmacol Ther. 1996;1(3):195-202. PubMed
- Andersson RG, Aberg G, Brattsand R, Ericsson E, Lundholm L. Studies on the mechanism of flush induced by nicotinic acid. Acta Pharmacol Toxicol (Copenh). 1977 Jul;41(1):1-10. PubMed
- Brown WV. Niacin for lipid disorders. Indications, effectiveness, and safety. Postgrad Med. 1995 Aug;98(2):185-9, 192-3. PubMed
- O'REILLY PO, CALLBECK MJ, HOFFER A. Sustained-release nicotinic acid (nicospan); effect on (1) cholesterol levels and (2) leukocytes. Can Med Assoc J. 1959;80(5):359-62.
- Gharavi AG, Diamond JA, Smith DA, Phillips RA. Niacin-induced myopathy. Am J Cardiol. 1994;74(8):841-2. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Fraunfelder FW, Fraunfelder FT, Illingworth DR. Adverse ocular effects associated with niacin therapy. Br J Ophthalmol 1995;79:54-56. PubMed
- Ali EH, McJunkin B, Jubelirer S, Hood W. Niacin induced coagulopathy as a manifestation of occult liver injury. W V Med J. 2013 Jan-Feb;109(1):12-4
- Aramwit P, Srisawadwong R, Supasyndh O. Effectiveness and safety of extended-release nicotinic acid for reducing serum phosphorus in hemodialysis patients. J Nephrol. 2012 May-Jun;25(3):354-62. PubMed
- Bassan M. A case for immediate-release niacin. Heart Lung. 2012 Jan-Feb;41(1):95-8. PubMed
- Davidson MH, Rooney M, Pollock E, Drucker J, Choy Y. Effect of colesevelam and niacin on low-density lipoprotein cholesterol and glycemic control in subjects with dyslipidemia and impaired fasting glucose. J Clin Lipidol. 2013 Sep-Oct;7(5):423-32. PubMed
- Guyton JR, Fazio S, Adewale AJ, Jensen E, Tomassini JE, Shah A, Tershakovec AM. Effect of extended-release niacin on new-onset diabetes among hyperlipidemic patients treated with ezetimibe/simvastatin in a randomized controlled trial. Diabetes Care. 2012 PubMed
- Loebl T, Raskin S. A novel case report: acute manic psychotic episode after treatment with niacin. J Neuropsychiatry Clin Neurosci. 2013 Fall;25(4):E14. PubMed
- Teo KK, Goldstein LB, Chaitman BR, Grant S, Weintraub WS, Anderson DC, Sila CA, Cruz-Flores S, Padley RJ, Kostuk WJ, Boden WE; AIM-HIGH Investigators. Extended-release niacin therapy and risk of ischemic stroke in patients with cardiovascular disease: the
- Goldie C, Taylor AJ, Nguyen P, McCoy C, Zhao XQ, Preiss D. Niacin therapy and the risk of new-onset diabetes: a meta-analysis of randomized controlled trials. Heart. 2016 Feb;102(3):198-203.
- Schandelmaier S, Briel M, Saccilotto R, Olu KK, Arpagaus A, Hemkens LG, Nordmann AJ. Niacin for primary and secondary prevention of cardiovascular events. Cochrane Database Syst Rev. 2017 Jun 14;6:CD009744. PubMed
- Jenkins DJA, Spence JD, Giovannucci EL, et al. Supplemental vitamins and minerals for CVD prevention and treatment. J Am Coll Cardiol 2018;71(22):2570-84. PubMed
- Song S, Lee CJ, Oh J, Park S, Kang SM, Lee SH. Effect of Niacin on Carotid Atherosclerosis in Patients at Low-Density Lipoprotein-Cholesterol Goal but High Lipoprotein (a) Level: a 2-Year Follow-Up Study. J Lipid Atheroscler. 2019;8(1):58-66. PubMed
- Kimura H, Umemori Y, Yuki D. Anaphylactic shock-like symptoms due to niacin overdose: A case report. J Dermatol 2022;49(8):e287-e288. PubMed
- Nawaz N, Mistretta T, Karime C, Lewis J, Wolf E. Cholestatic Drug-Induced Liver Injury in a Patient Taking High-Dose Niacin for Hyperlipidemia. J Investig Med High Impact Case Rep 2024;12:23247096231224349. PubMed
Maca 1 reference
- Valerio, L. G., Jr. and Gonzales, G. F. Toxicological aspects of the South American herbs cat's claw (Uncaria tomentosa) and Maca (Lepidium meyenii) : a critical synopsis. Toxicol.Rev 2005;24(1):11-35. PubMed
Tribulus 10 references
- Sharifi AM, Darabi R, Akbarloo N. Study of antihypertensive mechanism of Tribulus terrestris in 2K1C hypertensive rats: role of tissue ACE activity. Life Sci 2003;73:2963-71. PubMed
- Walker D, Bird A, Flora T, O'Sullivan B. Some effects of feeding Tribulus terrestris, Ipomoea lonchophylla and the seed of Abelmoschus ficulneus on fetal development and the outcome of pregnancy in sheep. Reprod Fertil Dev 1992;4:135-44. PubMed
- Al-Ali M, Wahbi S, Twaij H, Al-Badr A. Tribulus terrestris: preliminary study of its diuretic and contractile effects and comparison with Zea mays. J Ethnopharmacol 2003;85:257-60. PubMed
- Tabakova, P., Dimitrov, M., Ognyanov, K., and et al. Clinical study of Tribestan in females with endocrine sterility. Documentation for Registration (unpublished) 1999.
- Akhtari E, Raisi F, Keshavarz M, et al. Tribulus terrestris for treatment of sexual dysfunction in women: randomized double-blind placebo-controlled study. Daru 2014;22:40. PubMed
- Ryan M, Lazar I, Nadasdy GM, et al. Acute kidney injury and hyperbilirubinemia in a young male after ingestion of Tribulus terrestris. Clin Nephrol 2015;83(3):177-83. PubMed
- Postigo S, Lima SM, Yamada SS, et al. Assessment of the effects of Tribulus terrestris on sexual function of menopausal women. Rev Bras Ginecol Obstet 2016;38(3):140-6. PubMed
- Talasaz AH, Abbasi MR, Abkhiz S, Dashti-Khavidaki S. Tribulus terrestris-induced severe nephrotoxicity in a young healthy male. Nephrol Dial Tranplant 2010;25(11):3792-3. PubMed
- Samani NB, Jokar A, Soveid M, Heydari M, Mosavat SH. Efficacy of the hydroalcoholic extract of Tribulus terrestris on the serum glucose and lipid profile of women with diabetes mellitus: a double-blind randomized placebo-controlled clinical trial. J Evid
- Siddiqui MA, Itrat M, Mobeen A, Khan MI. Efficacy of khar-i-khasak (Tribulus terrestris Linn.) in prehypertension: a randomized, double-blind, placebo-controlled trial. J Complement Integr Med. 2021.
Asparagus 14 references
- The Review of Natural Products by Facts and Comparisons. St. Louis, MO: Wolters Kluwer Co., 1999.
- Electronic Code of Federal Regulations. Title 21. Part 182 -- Substances Generally Recognized As Safe. Available at: https://www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfcfr/CFRSearch.cfm?CFRPart=182
- Volz T, Berner D, Weigert C, et al. Fixed food eruption caused by asparagus. J Allergy Clin Immunol 2005;116:1390-2. PubMed
- Huang X, Kong L. Steroidal saponins from roots of Asparagus officinalis. Steroids 2006;71:171-6. PubMed
- Rodriguez R, Jaramillo S, Rodriguez G, et al. Antioxidant activity of ethanolic extracts from several asparagus cultivars. J Agric Food Chem 2005;53:5212-7. PubMed
- Rieker J, Ruzicka T, Neumann NJ, Homey B. Protein contact dermatitis to asparagus. J Allergy Clin Immunol 2004;113:354-5. PubMed
- Tabar AI, Alvarez-Puebla MJ, Gomez B, et al. Diversity of asparagus allergy: clinical and immunological features. Clin Exp Allergy 2004;34:131-6. PubMed
- Rademaker M, Yung A. Contact dermatitis to Asparagus officinalis. Australas J Dermatol 2000;41:262-3.
- Misico, R. I., Nicotra, V. E., Oberti, J. C., Barboza, G., Gil, R. R., and Burton, G. Withanolides and related steroids. Prog.Chem.Org.Nat.Prod. 2011;94:127-229.
- Hausen BM, Wolf C. 1,2,3-Trithiane-5-carboxylic acid, a first contact allergen from Asparagus officinalis (Liliaceae). Am J Contact Dermat 1996;7(1):41-46. PubMed
- Escribano MM, Munoz-Bellido FJ, Serrano P, et al. Acute urticaria after ingestion of asparagus. Allergy 1998;53(6):622-623. PubMed
- Chrubasik S, Droste C, Black A. Asparagus P(R) cannot compete with first-line diuretics in lowering the blood pressure in treatment-requiring antihypertensives. Phytother Res 2009;23:1345-6.
- Gaus BM, Scheiba N, Schäkel K. Asparagus-induced fixed food eruptions mimicking cutaneous lupus. Acta Derm Venereol 2014;94:731-2. PubMed
- Yanagi T, Shimizu H, Shimizu T. Occupational contact dermatitis caused by asparagus. Contact Dermatitis 2010;63:54. PubMed
Ginger 64 references
- Fischer-Rasmussen W, Kjaer SK, Dahl C, Asping U. Ginger treatment of hyperemesis gravidarum. Eur J Obstet Gynecol Reprod Biol 1991;38:19-24. PubMed
- Jewell D, Young G. Interventions for nausea and vomiting in early pregnancy. Cochrane Database Syst Rev 2000;(2):CD000145. PubMed
- Vutyavanich T, Kraisarin T, Ruangsri R. Ginger for nausea and vomiting in pregnancy: randomized, double-masked, placebo-controlled trial. Obstet Gynecol 2001;97:577-82. DOI
- Backon J. Ginger in preventing nausea and vomiting of pregnancy; a caveat due to its thromboxane synthetase activity and effect on testosterone binding. Eur J Obstet Gynecol Reprod Biol 1991;42:163-4. PubMed
- Srivastava KC. Effect of onion and ginger consumption on platelet thromboxane production in humans. Prostaglandins Leukot Essent Fatty Acids 1989;35:183-5. PubMed
- Stewart JJ, Wood MJ, Wood CD, Mims ME. Effects of ginger on motion sickness susceptibility and gastric function. Pharmacology 1991;42:111-20. PubMed
- Smith C, Crowther C, Willson K, et al. A randomized controlled trial of ginger to treat nausea and vomiting in pregnancy. Obstet Gynecol 2004;103:639-45. PubMed
- Portnoi G, Chng LA, Karimi-Tabesh L, et al. Prospective comparative study of the safety and effectiveness of ginger for the treatment of nausea and vomiting in pregnancy. Am J Obstet Gynecol 2003;189:1374-7.. PubMed
- Wigler I, Grotto I, Caspi D, Yaron M. The effects of Zintona EC (a ginger extract) on symptomatic gonarthritis. Osteoarthritis Cartilage 2003;11:783-9. PubMed
- Ghayur MN, Gilani AH. Ginger lowers blood pressure through blockade of voltage-dependent calcium channels. J Cardiovasc Pharmacol 2005;45:74-80. PubMed
- Thomson M, Al-Qattan KK, Al-Sawan SM, et al. The use of ginger (Zingiber officinale Rosc.) as a potential anti-inflammatory and antithrombotic agent. Prostaglandins Leukot Essent Fatty Acids 2002;67:475-8. PubMed
- Kanerva L, Estlander T, Jolanki R. Occupational allergic contact dermatitis from spices. Contact Dermatitis 1996;35:157-62. PubMed
- Akhani SP, Vishwakarma SL, Goyal RK. Anti-diabetic activity of Zingiber officinale in streptozotocin-induced type I diabetic rats. J Pharm Pharmacol 2004;56:101-5.
- Kruth P, Brosi E, Fux R, et al. Ginger-associated overanticoagulation by phenprocoumon. Ann Pharmacother 2004;38:257-60. PubMed
- Jiang X, Williams KM, Liauw WS, et al. Effect of ginkgo and ginger on the pharmacokinetics and pharmacodynamics of warfarin in healthy subjects. Br J Clin Pharmacol 2005;59:425-32. PubMed
- Borrelli F, Capasso R, Aviello G, et al. Effectiveness and safety of ginger in the treatment of pregnancy-induced nausea and vomiting. Obstet Gynecol 2005;105:849-56. PubMed
- Smith C, Crowther C, Wilson K et al. A randomized controlled trial of ginger to treat nausea and vomiting in pregnancy. Obstet Gynecol 2004;103:639-45. PubMed
- Jiang X, Blair EY, McLachlan AJ. Investigation of the effects of herbal medicines on warfarin response in healthy subjects: a population pharmacokinetic-pharmacodynamic modeling approach. J Clin Pharmacol 2006;46:1370-8. PubMed
- Chittumma P, Kaewkiattikun K, Wiriyasiriwach B. Comparison of the effectiveness of ginger and vitamin B6 for treatment of nausea and vomiting in early pregnancy: a randomized double-blind controlled trial. J Med Assoc Thai 2007;90:15-20.
- Ozgoli G, Goli M, Moattar F. Comparison of effects of ginger, mefenamic acid, and ibuprofen on pain in women with primary dysmenorrhea. J Altern Complement Med 2009;15:129-32. PubMed
- Black CD, Herring MP, Hurley DJ, O'Connor PJ. Ginger (Zingiber officinale) reduces muscle pain caused by eccentric exercise. J Pain 2010;11:894-903. PubMed
- Heitmann K, Nordeng H, Holst L. Safety of ginger use in pregnancy: results from a large population-based cohort study. Eur J Clin Pharmacol 2012 Jun 17. PubMed
- Ryan JL, Heckler CE, Roscoe JA, et al. Ginger (Zingiber officinale) reduces acute chemotherapy-induced nausea: a URCC CCOP study of 576 patients. Support Care Cancer. 2012;20:1479-89. PubMed
- Backon J. Ginger as an antiemetic: possible side effects due to its thromboxane synthetase activity. Anaesthesia. 1991;46(8):705-6.. PubMed
- Abebe W. Herbal medication: potential for adverse interactions with analgesic drugs. J Clin Pharm Ther. 2002;27:391-401. PubMed
- Argento A, Tiraferri E, Marzaloni M. [Oral anticoagulants and medicinal plants. An emerging interaction]. Ann Ital Med Int. 2000;15:139-43.
- Young HY, Liao JC, Chang YS, et al. Synergistic effect of ginger and nifedipine on human platelet aggregation: a study in hypertensive patients and normal volunteers. Am J Chin Med. 2006;34:545-51. PubMed
- Greenway FL, Liu Z, Martin CK, et al. Safety and efficacy of NT, an herbal supplement, in treating human obesity. Int J Obes (Lond). 2006;30:1737-41. PubMed
- Shalansky S, Lynd L, Richardson K, et al. Risk of warfarin-related bleeding events and supratherapeutic international normalized ratios associated with complementary and alternative medicine: a longitudinal analysis. Pharmacotherapy. 2007;27:1237-47. PubMed
- Lesho EP, Saullo L, Udvari-Nagy S. A 76-year-old woman with erratic anticoagulation. Cleve Clin J Med. 2004;71:651-6. PubMed
- Okonta JM, Uboh M, Obonga WO. Herb-Drug Interaction: A Case Study of Effect of Ginger on the Pharmacokinetic of Metronidazole in Rabbit. Indian Journal of Pharmaceutical Sciences (India) 2008;70(230):232. PubMed
- Chiang HM, Chao PD, Hsiu SL, et al. Ginger significantly decreased the oral bioavailability of cyclosporine in rats. Am J Chin Med. 2006;34:845-55. PubMed
- Bhandari U, Kanojia R, Pillai KK. Effect of ethanolic extract of Zingiber officinale on dyslipidaemia in diabetic rats. J Ethnopharmacol. 2005;97:227-30. PubMed
- Ojewole JA. Analgesic, antiinflammatory and hypoglycaemic effects of ethanol extract of Zingiber officinale (Roscoe) rhizomes (Zingiberaceae) in mice and rats. Phytother Res. 2006;20:764-72.
- Al-Amin ZM, Thomson M, Al-Qattan KK, et al. Anti-diabetic and hypolipidaemic properties of ginger (Zingiber officinale) in streptozotocin-induced diabetic rats. Br J Nutr. 2006;96:660-6.
- Islam MS, Choi H. Comparative effects of dietary ginger (Zingiber officinale) and garlic (Allium sativum) investigated in a type 2 diabetes model of rats. J Med Food. 2008;11:152-9.
- Cady RK, Goldstein J, Nett R, et al. A double-blind placebo-controlled pilot study of sublingual feverfew and ginger (LipiGesic M) in the treatment of migraine. Headache 2011;51:1078-86.
- Futrell, J. M. and Rietschel, R. L. Spice allergy evaluated by results of patch tests. Cutis 1993;52(5):288-290.
- Sripramote, M. and Lekhyananda, N. A randomized comparison of ginger and vitamin B6 in the treatment of nausea and vomiting of pregnancy. J Med Assoc.Thai. 2003;86(9):846-853.
- Lohsiriwat, S., Rukkiat, M., Chaikomin, R., and Leelakusolvong, S. Effect of ginger on lower esophageal sphincter pressure. J.Med.Assoc.Thai. 2010;93(3):366-372.
- Liu, P. H. and Ho, H. L. Ginger and drug bezoar induced small bowel obstruction. J R.Coll.Surg.Edinb. 1983;28(6):397-398.
- Maghbooli M, Golipour F, Moghimi Esfandabadi A, Yousefi M. Comparison between the efficacy of ginger and sumatriptan in the ablative treatment of the common migraine. Phytother Res 2014;28(3):412-5. PubMed
- Mahluji S, Attari VE, Mobasseri M, Payahoo L, Ostadrahimi A, Golzari SE. Effects of ginger (Zingiber officinale) on plasma glucose level, HbA1c and insulin sensitivity in type 2 diabetic patients. Int J Food Sci Nutr 2013;64(6):682-6.
- Mozaffari-Khosravi H, Talaei B, Jalali BA, Najarzadeh A, Mozayan MR. The effect of ginger powder supplementation on insulin resistance and glycemic indices in patients with type 2 diabetes: a randomized, double-blind, placebo-controlled trial. Complement PubMed
- Paramdeep G. Efficacy and tolerability of ginger (Zingiber officinale) in patients of osteoarthritis of knee. Indian J Physiol Pharmacol 2013;57(2):177-83.
- Rahnama P, Montazeri A, Huseini HF, Kianbakht S, Naseri M. Effect of Zingiber officinale R. rhizomes (ginger) on pain relief in primary dysmenorrhea: a placebo randomized trial. BMC Complement Altern Med 2012;12:92. PubMed
- Viljoen E, Visser J, Koen N, Musekiwa A. A systematic review and meta-analysis of the effect and safety of ginger in the treatment of pregnancy-associated nausea and vomiting. Nutr J 2014;13:20. PubMed
- Bartels EM, Folmer VN, Bliddal H, et al. Efficacy and safety of ginger in osteoarthritis patients: a meta-analysis of randomized placebo-controlled trials. Osteoarthritis Cartilage. 2015;23(1):13-21. PubMed
- Choi JS, Han JY, Ahn HK, et al. Assessment of fetal and neonatal outcomes in the offspring of women who had been treated with dried ginger (Zingiberis rhizoma siccus) for a variety of illnesses during pregnancy. J Obstet Gynaecol. 2015;35(2):125-30.
- Marx W, McKavanagh D, McCarthy AL, Bird R, Ried K, Chan A, Isenring L. The effect of ginger (Zingiber officinale) on platelet aggregation: A systematic literature review. PLoS One. 2015;10(10):e0141119. PubMed
- Crichton M, Marshall S, Marx W, McCarthy AL, Isenring E. Efficacy of ginger (Zingiber officinale) in ameliorating chemotherapy-induced nausea and vomiting and chemotherapy-related outcomes: A systematic review update and meta-analysis. J Acad Nutr Diet. 2 PubMed
- Martins LB, Rodrigues AMDS, Monteze NM, et al. Double-blind placebo-controlled randomized clinical trial of ginger (Zingiber officinale Rosc.) in the prophylactic treatment of migraine. Cephalalgia. 2020;40(1):88-95.
- Martins LB, Rodrigues AMDS, Rodrigues DF, Dos Santos LC, Teixeira AL, Ferreira AVM. Double-blind placebo-controlled randomized clinical trial of ginger (Zingiber officinale Rosc.) addition in migraine acute treatment. Cephalalgia. 2019;39(1):68-76.
- Ahad A, Raish M, Bin Jardan YA, Alam MA, Al-Mohizea AM, Al-Jenoobi FI. Effect of Hibiscus sabdariffa and Zingiber officinale on the antihypertensive activity and pharmacokinetic of losartan in hypertensive rats. Xenobiotica. 2020:1-11.
- Okuhira H, Nakatani Y, Furukawa F, Kanazawa N. Anaphylaxis to ginger induced by herbal medicine. Allergol Int. 2020;69(1):159-160. PubMed
- Yamprasert R, Chanvimalueng W, Mukkasombut N, Itharat A. Ginger extract versus Loratadine in the treatment of allergic rhinitis: a randomized controlled trial. BMC Complement Med Ther. 2020;20(1):116. PubMed
- Ebrahimzadeh A, Ebrahimzadeh A, Mirghazanfari SM, Hazrati E, Hadi S, Milajerdi A. The effect of ginger supplementation on metabolic profiles in patients with type 2 diabetes mellitus: a systematic review and meta-analysis of randomized controlled trials. PubMed
- Alam MA, Bin Jardan YA, Alzenaidy B, et al. Effect of Hibiscus sabdariffa and Zingiber officinale on pharmacokinetics and pharmacodynamics of amlodipine. J Pharm Pharmacol 2021;73(9):1151-60.
- Akbarzadeh E, Heydari M, Atarzadeh F, Jaladat AM. Chronic dysuria following ginger (Zingiber officinale) use: a case report. Galen Med J 2018;7:e1086. DOI
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Rostamkhani H, Veisi P, Niknafs B, Jafarabadi MA, Ghoreishi Z. The effect of zingiber officinale on prooxidant-antioxidant balance and glycemic control in diabetic patients with ESRD undergoing hemodialysis: a double-blind randomized control trial. BMC Co PubMed
- Husain I, Dale OR, Idrisi M, et al. Evaluation of the Herb-Drug Interaction (HDI) Potential of Zingiber officinale and Its Major Phytoconstituents. J Agric Food Chem. 2023;71(19):7521-7534.
- Committee on Practice Bulletins-Obstetrics. ACOG Practice Bulletin No. 189: Nausea And Vomiting Of Pregnancy. Obstet Gynecol. 2018;131(1):e15-e30. PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
Damiana 2 references
- Newall CA, Anderson LA, Philpson JD. Herbal Medicine: A Guide for Healthcare Professionals. London, UK: The Pharmaceutical Press, 1996.
- Alarcon-Aquilar FJ, Roman-Ramos R, Perez-Gutierrez S, et al. Study of the anti-hyperglycemic effect of plants used as antidiabetics. J Ethnopharmacol 1998;61:101-10. PubMed
Dong Quai 19 references
- Hirata JD, Swiersz LM, Zell B, et al. Does dong quai have estrogenic effects in postmenopausal women? A double-blind, placebo-controlled trial. Fertil Steril 1997;68:981-6. PubMed
- Page RL II, Lawrence JD. Potentiation of warfarin by dong quai. Pharmacotherapy 1999;19:870-6. PubMed
- Heck AM, DeWitt BA, Lukes AL. Potential interactions between alternative therapies and warfarin. Am J Health Syst Pharm 2000;57:1221-7. DOI
- Eagon PK, Elm MS, Hunter DS, et al. Medicinal herbs: modulation of estrogen action. Era of Hope Mtg, Dept Defense; Breast Cancer Res Prog, Atlanta, GA 2000;Jun 8-11.
- Dr. Duke's Phytochemical and Ethnobotanical Databases. Available at: http://www.ars-grin.gov/duke/.
- Amato P, Christophe S, Mellon PL. Estrogenic activity of herbs commonly used as remedies for menopausal symptoms. Menopause 2002;9:145-50. PubMed
- Shi M, Chang L, He G. [Stimulating action of Carthamus tinctorius L., Angelica sinensis (Oliv.) Diels and Leonurus sibiricus L. on the uterus]. Zhongguo Zhong Yao Za Zhi 1995;20:173-5, 192.
- Hoult JR, Paya M. Pharmacological and biochemical actions of simple coumarins: natural products with therapeutic potential. Gen Pharmacol 1996;27:713-22.. PubMed
- Cheong JL, Bucknall R. Retinal vein thrombosis associated with a herbal phytoestrogen preparation in a susceptible patient. Postgrad Med J 2005;81:266-7.. PubMed
- Chang CJ, Chiu JH, Tseng LM, et al. Modulation of HER2 expression by ferulic acid on human breast cancer MCF7 cells. Eur J Clin Invest 2006;36:588-96. PubMed
- Chuang CH, Doyle P, Wang JD, et al. Herbal medicines used during the first trimester and major congenital malformations: an analysis of data from a pregnancy cohort study. Drug Saf 2006;29:537-48. PubMed
- Lau CBS, Ho TCY, Chan TWL, Kim SCF. Use of dong quai (Angelica sinensis) to treat peri- and postmenopausal symptoms in women with breast cancer: is it appropriate? Menopause 2005;12:734-40.
- Ellis GR, Stephens MR. Untitled (photograph and a brief case report). BMJ 1999;319:650.
- Nambiar, S., Schwartz, R. H., and Constantino, A. Hypertension in mother and baby linked to ingestion of Chinese herbal medicine. West J Med 1999;171(3):152.
- Lee, S. K., Cho, H. K., Cho, S. H., Kim, S. S., Nahm, D. H., and Park, H. S. Occupational asthma and rhinitis caused by multiple herbal agents in a pharmacist. Ann.Allergy Asthma Immunol. 2001;86(4):469-474. PubMed
- Xu, J. and Li, G. [Observation on short-term effects of Angelica injection on chronic obstructive pulmonary disease patients with pulmonary hypertension]. Zhongguo Zhong Xi Yi Jie He Za Zhi 2000;20(3):187-189.
- Scott, G. N. and Elmer, G. W. Update on natural product--drug interactions. Am J Health Syst.Pharm 2-15-2002;59(4):339-347. PubMed
- Circosta, C., Pasquale, R. D., Palumbo, D. R., Samperi, S., and Occhiuto, F. Estrogenic activity of standardized extract of Angelica sinensis. Phytother.Res. 2006;20(8):665-669.
- Fung FY, Wong WH, Ang SK, et al. A randomized, double-blind, placebo- controlled study on the anti-haemostatic effects of Curcuma longa, Angelica sinensis and Panax ginseng. Phytomedicine. 2017;32:88-96. PubMed
Vitamin A 31 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Griffiths JK. The vitamin A paradox. J Pediatr 2000;137:604-7.. PubMed
- Hardman JG, Limbird LL, Molinoff PB, eds. Goodman and Gillman's The Pharmacological Basis of Therapeutics, 9th ed. New York, NY: McGraw-Hill, 1996.
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- FDA Talk Paper. Vitamin A and birth defects (T95-56). Food and Drug Administration, U.S. Department of Health and Human Services, Rockville, MD. October 6, 1995.
- Russell RM. The vitamin A spectrum: from deficiency to toxicity. Am J Clin Nutr 2000;71:878-84. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Feskanich D, Singh V, Willett WC, Colditz GA. Vitamin A intake and hip fractures among postmenopausal women. JAMA 2002;287:47-54. PubMed
- Melhus H, Michaelsson K, Kindmark A, et al. Excessive dietary intake of vitamin A is associated with reduced bone mineral density and increased risk for hip fracture. Ann Intern Med 1998;129:770-8. PubMed
- Michaelsson K, Lithell H, Vessby B, Melhus H. Serum retinol levels and the risk of fracture. N Engl J Med 2003;348:287-94.. PubMed
- Botterweck AA, van den Brandt PA, Goldbohm RA. Vitamins, carotenoids, dietary fiber, and the risk of gastric carcinoma: results from a prospective study after 6.3 years of follow-up. Cancer 2000;88:737-48.. DOI
- Meyskens FL Jr, Graham V, Chvapil M, et al. A phase I trial of beta-all-trans-retinoic acid delivered via a collagen sponge and a cervical cap for mild or moderate intraepithelial cervical neoplasia. J Natl Cancer Inst 1983;71:921-5..
- Hathcock JN, Hattan DG, Jenkins MY, et al. Evaluation of vitamin A toxicity. Am J Clin Nutr 1990;52:183-202.. PubMed
- Walters BN, Gubbay SS. Tetracycline and benign intracranial hypertension: report of five cases. Br Med J 1981;282:19-20.. PubMed
- Pearson MG, Littlewood SM, Bowden AN. Tetracycline and benign intracranial hypertension (letter). Br Med J 1981;282:568-9.. PubMed
- Azais-Braesco V, Pascal G. Vitamin A in pregnancy: requirements and safety limits. Am J Clin Nutr 2000;71:1325S-33S. PubMed
- Smedts HP, de Vries JH, Rakhshandehroo M, et al. High maternal vitamin E intake by diet or supplements is associated with congenital heart defects in the offspring. BJOG 2009;116:416-23. PubMed
- Grotto, I., Mimouni, M., Gdalevich, M., and Mimouni, D. Vitamin A supplementation and childhood morbidity from diarrhea and respiratory infections: a meta-analysis. J Pediatr 2003;142(3):297-304. PubMed
- Mahalanabis, D., Lahiri, M., Paul, D., Gupta, S., Gupta, A., Wahed, M. A., and Khaled, M. A. Randomized, double-blind, placebo-controlled clinical trial of the efficacy of treatment with zinc or vitamin A in infants and young children with severe acute l
- Long, K. Z., Montoya, Y., Hertzmark, E., Santos, J. I., and Rosado, J. L. A double-blind, randomized, clinical trial of the effect of vitamin A and zinc supplementation on diarrheal disease and respiratory tract infections in children in Mexico City, Mex
- Fritz, H., Kennedy, D., Fergusson, D., Fernandes, R., Doucette, S., Cooley, K., Seely, A., Sagar, S., Wong, R., and Seely, D. Vitamin A and retinoid derivatives for lung cancer: a systematic review and meta analysis. PLoS.One. 2011;6(6):e21107. PubMed
- Mayo-Wilson, E., Imdad, A., Herzer, K., Yakoob, M. Y., and Bhutta, Z. A. Vitamin A supplements for preventing mortality, illness, and blindness in children aged under 5: systematic review and meta-analysis. BMJ 2011;343:d5094. PubMed
- Mazumder S, Taneja S, Bhatia K, Yoshida S, Kaur J, Dube B, Toteja GS, Bahl R, Fontaine O, Martines J, Bhandari N; Neovita India Study Group. Efficacy of early neonatal supplementation with vitamin A to reduce mortality in infancy in Haryana, India (Neovit
- Baineni R, Gulati R, Delhi CK. Vitamin A toxicity presenting as bone pain. Arch Dis Child. 2017;102(6):556-8. PubMed
- Darlow BA, Graham PJ, Rojas-Reyes MX. Vitamin A supplementation to prevent mortality and short- and long-term morbidity in very low birth weight infants. Cochrane Database Syst Rev. 2016;(8):CD000501. PubMed
- Haider BA, Sharma R, Bhutta ZA. Neonatal vitamin A supplementation for the prevention of mortality and morbidity in term neonates in low and middle income countries. Cochrane Database Syst Rev. 2017;2:CD006980. PubMed
- Mohammad YM, Raslan IR, Al-Hussain FA. Idiopathic Intracranial Hypertension Induced by Topical Application of Vitamin A. J Neuroophthalmol. 2016;36(4):412-3. PubMed
- Masnadi Shirazi K, Nikniaz Z, Masnadi Shirazi A, Rohani M. Vitamin A supplementation decreases disease activity index in patients with ulcerative colitis: A randomized controlled clinical trial. Complement Ther Med. 2018 Dec;41:215-219. PubMed
- Ding Y, Hu P, Yang Y, et al. Impact of maternal daily oral low-dose vitamin A supplementation on the mother-infant pair: a randomised placebo-controlled trial in China. Nutrients 2021;13(7):2370. PubMed
- Knapik JJ, Hoedebecke SS. Vitamin A and bone fractures: systematic review and meta-analysis. J Spec Oper Med 2021;21(2):100-7. PubMed
- Imdad A, Mayo-Wilson E, Haykal MR, et al. Vitamin A supplementation for preventing morbidity and mortality in children from six months to five years of age. Cochrane Database Syst Rev 2022;3(3):CD008524. PubMed
Cowhage 12 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Anon. Epidemiological notes and reports: Mucuna pruriens-associated pruritus--New Jersey. MMWR Morb Mortal Wkly Rep 1985;34:732-3.
- HP-200 in Parkinson's Disease study group. An alternative medicine treatment for Parkinson's disease: Results of a multicenter clinical trial. J Alt Comp Med 1995;1:249-55. DOI
- Infante ME, Perez AM, Simao MR, et al. Outbreak of acute toxic psychosis attributed to Mucuna pruriens. Lancet 1990;336:1129. PubMed
- Vaidya AB, Rajagopalan TG, Mankodi NA, et al. Treatment of Parkinson's disease with the cowhage plant-Mucuna pruriens Bak. Neurol India 1978;26:171-6.
- Vadivel V, Janardhanan K. Nutritional and anti-nutritional composition of velvet bean: an under-utilized food legume in south India. Int J Food Sci Nutr 2000;51:279-87. PubMed
- Akhtar MS, Qureshi AQ, Iqbal J. Antidiabetic evaluation of Mucuna pruriens, Linn seeds. J Pak Med Assoc 1990;40:147-50.
- Prakash, D., Niranjan, A., and Tewari, S. K. Some nutritional properties of the seeds of three Mucuna species. Int.J.Food Sci.Nutr. 2001;52(1):79-82.
- Vadivel, V. and Janardhanan, K. Nutritional and antinutritional characteristics of seven South Indian wild legumes. Plant Foods Hum.Nutr 2005;60(2):69-75. PubMed
- Creapure (Creatine Monohydrate). Toxicological Datasheet. Degussa BioActives. Available at: https://www.fda.gov/ohrms/DOCKETS/.../95s-0316-rpt0154-54-Ref-50-vol112.pdf.
- Pulikkalpura H, Kurup R, Mathew PJ, Baby S. Levodopa in Mucuna pruriens and its degradation. Sci Rep 2015;5:11078. PubMed
Muira Puama 2 references
- Waynberg, J. and Brewer, S. Effects of Herbal vX on libido and sexual activity in premenopausal and postmenopausal women. Adv Ther 2000;17(5):255-262. PubMed
- Nguyen S, Rajfer J, Shaheen M. Safety and efficacy of daily Revactin in men with erectile dysfunction: a 3-month pilot study. Transl Androl Urol. 2018;7(2):266-73. PubMed
Sarsaparilla 3 references
- Blumenthal M, ed. The Complete German Commission E Monographs: Therapeutic Guide to Herbal Medicines. Trans. S. Klein. Boston, MA: American Botanical Council, 1998.
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- Vandenplas O, Depelchin S, Toussaint G, et al. Occupational asthma caused by sarsaparilla root dust. J Allergy Clin Immunol 1996;97:1416-8. PubMed
Pantothenic Acid 11 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Debourdeau PM, Djezzar S, Estival JL, et al. Life-threatening eosinophilic pleuropericardial effusion related to vitamins B5 and H. Ann Pharmacother 2001;35:424-6. DOI
- Schmuth, M., Wimmer, M. A., Hofer, S., Sztankay, A., Weinlich, G., Linder, D. M., Elias, P. M., Fritsch, P. O., and Fritsch, E. Topical corticosteroid therapy for acute radiation dermatitis: a prospective, randomized, double-blind study. Br.J.Dermatol. 2 PubMed
- Schreck, U., Paulsen, F., Bamberg, M., and Budach, W. Intraindividual comparison of two different skin care conceptions in patients undergoing radiotherapy of the head-and-neck region. Creme or powder? Strahlenther.Onkol. 2002;178(6):321-329. PubMed
- Herbst, R. A., Uter, W., Pirker, C., Geier, J., and Frosch, P. J. Allergic and non-allergic periorbital dermatitis: patch test results of the Information Network of the Departments of Dermatology during a 5-year period. Contact Dermatitis 2004;51(1):13-1 PubMed
- Champault, G. and Patel, J. C. [Treatment of constipation with Bepanthene]. Med.Chir Dig. 1977;6(1):57-59.
- Scott LN, Fiume M, Bergfeld WF, et al. Safety Assessment of Panthenol, Pantothenic Acid, and Derivatives as Used in Cosmetics. Int J Toxicol 2022;41(3_suppl):77-128. PubMed
- Han J, Warshaw EM. Allergic Contact Dermatitis to Panthenol in "Hypoallergenic" Products. Dermatitis 2023;34(1):62-63. PubMed
- Blanchard G, Kerre S, Walker A, et al. Allergic contact dermatitis from pantolactone and dexpanthenol in wound healing creams. Contact Dermatitis 2022;87(5):468-471. PubMed
- Peltier E, Trapp S, de Salvo R, et al. A new dexpanthenol-containing liquid cleanser for atopic-prone skin: Results from two prospective clinical studies evaluating cutaneous tolerability, moisturization potential, and effects on barrier function. J Cosme PubMed
Ashwagandha 32 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Upton R, ed. Ashwagandha Root (Withania somnifera): Analytical, quality control, and therapuetic monograph. Santa Cruz, CA: American Herbal Pharmacopoeia 2000:1-25.
- Davis L, Kuttan G. Effect of Withania somnifera on cyclophosphamide-induced urotoxicity. Cancer Lett 2000;148:9-17. PubMed
- Davis L, Kuttan G. Suppressive effect of cyclophosphamide-induced toxicity by Withania somnifera extract in mice. J Ethnopharmacol 1998;62:209-14. PubMed
- Mishra LC, Singh BB, Dagenais S. Scientific basis for the therapeutic use of Withania somnifera (ashwagandha): a review. Altern Med Rev 2000;5:334-46. DOI
- Andallu B, Radhika B. Hypoglycemic, diuretic and hypocholesterolemic effect of winter cherry (Withania somnifera, Dunal) root. Indian J Exp Biol 2000;38:607-9.
- Kulkarni RR, Patki PS, Jog VP, et al. Treatment of osteoarthritis with a herbomineral formulation: a double-blind, placebo-controlled, cross-over study. J Ethnopharmacol 1991;33:91-5. PubMed
- Ahumada F, Aspee F, Wikman G, Hancke J. Withania somnifera exract. Its effects on arterial blood pressure in anaesthetized dogs. Phytother Res 1991;5:111-14.
- Panda S, Kar A. Withania somnifera and Bauhinia purpurea in the regulation of circulating thyroid hormone concentrations in female mice. J Ethnopharmacol 1999;67:233-39. PubMed
- Panda S, Kar A. Changes in thyroid hormone concentrations after administration of ashwagandha root extract to adult male mice. J Pharm Pharmacol 1998;50:1065-68. PubMed
- Sehgal, V. N., Verma, P., and Bhattacharya, S. N. Fixed-drug eruption caused by ashwagandha (Withania somnifera): a widely used Ayurvedic drug. Skinmed. 2012;10(1):48-49.
- Agnihotri AP, Sontakke SD, Thawani VR, Saoji A, Goswami VS. Effects of Withania somnifera in patients of schizophrenia: a randomized, double blind, placebo controlled pilot trial study. Indian J Pharmacol. 2013;45(4):417-8. PubMed
- Biswal BM, Sulaiman SA, Ismail HC, Zakaria H, Musa KI. Effect of Withania somnifera (Ashwagandha) on the development of chemotherapy-induced fatigue and quality of life in breast cancer patients. Integr Cancer Ther. 2013;12(4):312-22.
- Sharma AK, Basu I, Singh S. Efficacy and safety of Ashwagandha root extract in subclinical hypothyroid patients: a double-blind, randomized placebo-controlled trial. J Altern Complement Med. 2018 Mar;24(3):243-248. PubMed
- Durg S, Bavage S, Shivaram SB. Withania somnifera (Indian ginseng) in diabetes mellitus: A systematic review and meta-analysis of scientific evidence from experimental research to clinical application. Phytother Res. 2020;34(5):1041-1059.
- Björnsson HK, Björnsson ES, Avula B, et al. Ashwagandha-induced liver injury: A case series from Iceland and the US Drug-Induced Liver Injury Network. Liver Int. 2020;40(4):825-829. PubMed
- Tharakan A, Shukla H, Benny IR, Tharakan M, George L, Koshy S. Immunomodulatory Effect of Withania somnifera (Ashwagandha) Extract-A Randomized, Double-Blind, Placebo Controlled Trial with an Open Label Extension on Healthy Participants. J Clin Med 2021;1 PubMed
- Ireland PJ, Hardy T, Burt AD, Donnelly MC. Drug-induced hepatocellular injury due to herbal supplement ashwagandha. J R Coll Physicians Edinb. 2021;51(4):363-365. PubMed
- Kamal HI, Patel K, Brdak A, Heffernan J, Ahmad N. Ashwagandha as a unique cause of thyrotoxicosis presenting with supraventricular tachycardia. Cureus. 2022 Mar 25;14(3):e23494. PubMed
- Suryawanshi G, Abdallah M, Thomson M, Desai N, Chauhan A, Lim N. Ashwagandha-Associated Acute Liver Failure Requiring Liver Transplantation. Am J Ther 2023;30(1):e80-e83. PubMed
- Pusec CM, Wolsky R, Llerena C, Sura P. A Case of Supplement-Induced Hepatitis. Cureus 2022;14(10):e30433. PubMed
- Ajgaonkar A, Jain M, Debnath K. Efficacy and Safety of Ashwagandha (Withania somnifera) Root Extract for Improvement of Sexual Health in Healthy Women: A Prospective, Randomized, Placebo-Controlled Study. Cureus 2022;14(10):e30787. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Lubarska M, Halasinski P, Hryhorowicz S, et al. Liver Dangers of Herbal Products: A Case Report of Ashwagandha-Induced Liver Injury. Int J Environ Res Public Health 2023;20(5):3921. PubMed
- Tóth M, Benedek AE, Longerich T, Seitz HK. Ashwagandha-induced acute liver injury: A case report. Clin Case Rep 2023;11(3):e7078.
- Bokan G, Glamocanin T, Mavija Z, et al. Herb-Induced Liver Injury by Ayurvedic Ashwagandha as Assessed for Causality by the Updated RUCAM: An Emerging Cause. Pharmaceuticals (Basel) 2023;16(8):1129. PubMed
- Patel PA, Sanborn E, Then R, Williams DM. Recurrent Reversible Cerebral Vasoconstriction Syndrome: A Report of Two Cases. Cureus 2023;15(8):e42992. PubMed
- Majeed M, Nagabhushanam K, Murali A, Vishwanathan DT, Mamidala RV, Mundkur L. A Standardized Withania somniferra (Linn.) Root Extract with Piperine Alleviates the Symptoms of Anxiety and Depression by Increasing Serotonin Levels: A Double-Blind, Randomize
- Philips CA, Valsan A, Theruvath AH, et al. Ashwagandha-induced liver injury-A case series from India and literature review. Hepatol Commun 2023;7(10):e0270. PubMed
- Hayashi M, Hamada H, Azuma SI, Hayashi K. Painless Thyroiditis by Withania somnifera (Ashwagandha). Cureus 2024;16(3):e55352. PubMed
- Vazirani S, Kothari A, Fujimoto J, Gomez M. Supplements Are Not a Synonym for Safe: Suspected Liver Injury From Ashwagandha. Fed Pract 2023;40(9):315-319. PubMed
- Patel M, Newell R, Hillier M, Ramalingam R. Herbal remedies as a potential cause of hypoadrenalism. Br J Hosp Med (Lond) 2024;85(6):1-4. PubMed
Sea Buckthorn 7 references
- Johansson AK, Korte H, Yang B, et al. Sea buckthorn berry oil inhibits platelet aggregation. J Nutr Biochem 2000;11:491-5.. PubMed
- Grad, S. C., Muresan, I., and Dumitrascu, D. L. Generalized yellow skin caused by high intake of sea buckthorn. Forsch.Komplementmed. 2012;19(3):153-156. PubMed
- Vlasov, V. V. [Hippophae oil in the treatment of superficial skin burns]. Vestn.Dermatol Venerol. 1970;44(6):69-72.
- Chang BB, Wang F Xu TY Zhang QQ He J Zhang XJ Li J. Total flavones of Hippophae rhamnoides L. for essential hypertension: a systematic review of randomized controlled trials. Chinese Journal of Evidence-Based Medicine. 2009;9(11):1207-1213. DOI
- Olas B, Kontek B, Szczesna M, et al. Inhibition of blood platelet adhesion by phenolics rich fraction of Hippophae rhamnoides L. fruits. J Physiol Pharmacol. 2017;68(2):223-9.
- Larmo P, Järvinen R, Laihia J, et al. Effects of a sea buckthorn oil spray emulsion on dry eye. Cont Lens Anterior Eye. 2019;42(4):428-433. PubMed
- De Seta F, Caruso S, Di Lorenzo G, Romano F, Mirandola M, Nappi RE. Efficacy and safety of a new vaginal gel for the treatment of symptoms associated with vulvovaginal atrophy in postmenopausal women: A double-blind randomized placebo-controlled study. Ma PubMed
Horny Goat Weed 11 references
- Cirigliano MD, Szapary PO. Horny goat weed for erectile dysfunction. Alt Med Alert 2001;4:19-22.
- Partin JF, Pushkin YR. Tachyarrhythmia and hypomania with horny goat weed. Psychosomatics 2004;45:536-7. PubMed
- De Naeyer A, Pocock V, Milligan S, De Keukeleire D. Estrogenic activity of a polyphenolic extract of the leaves of Epimedium brevicornum. Fitoterapia 2005;76:35-40. PubMed
- Zhang CZ, Wang SX, Zhang Y, et al. In vitro estrogenic activities of Chinese medicinal plants traditionally used for the management of menopausal symptoms. J Ethnopharmacol 2005;98:295-300. PubMed
- Yap SP, Shen P, Li J, et al. Molecular and pharmacodynamic properties of estrogenic extracts from the traditional Chinese medicinal herb, Epimedium. J Ethnopharmacol 2007;113:218-24. PubMed
- Yan, F. F., Liu, Y., Liu, Y. F., and Zhao, Y. X. Herba Epimedii water extract elevates estrogen level and improves lipid metabolism in postmenopausal women. Phytother.Res. 2008;22(9):1224-1228. PubMed
- Ramanathan VS, Mitropoulos E, Shlopov B, et al. An Enzyte'ing' case of acute hepatitis. J Clin Gastroenterol 2011;45(9):834-5. PubMed
- Zhong Q, Shi Z, Zhang L, et al. The potential of Epimedium koreanum Nakai for herb-drug interaction. J Pharm Pharmacol 2017;69(10):1398-408. doi: 10.1111/jphp.12773.
- Irfan M, Kwon TH, Lee DH, et al. Antiplatelet and Antithrombotic Effects of Epimedium koreanum Nakai. Evid Based Complement Alternat Med. Apr 2021;2021:7071987. PubMed
- Tan K, Yang W, Pang L, Hou F. Differences in clinical characteristics among 726 patients with Chinese herbal medicine- or Western medicine-induced liver injury. Medicine (Baltimore) 2022;101(32):e29909. PubMed
- Li K, Yu XH, Maskey AR, et al. Cytochrome P450 3A4 suppression by epimedium and active compound kaempferol leads to synergistic anti-inflammatory effect with corticosteroid. Front Pharmacol 2023;13:1042756. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC