
pH Balance Ingredients & Drug Interactions
What is this page for?
First and foremost: checking pH Balance against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
pH Balance is a dietary supplement by Theramedix BioSET with 19 active ingredients. Its ingredients are commonly taken for replacing fluids and electrolytes, preventing dehydration during exercise or illness, treating low blood sodium (under medical care).Based on those ingredients, 2,184 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Marshmallow, Ginger, Rosemary. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against pH Balance by Theramedix BioSET
Ask about any prescription or over-the-counter medication and we check it for interactions with pH Balance by Theramedix BioSET — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of pH Balance by Theramedix BioSET
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Low disclosure
pH Balance contains 19 ingredients, including several minerals and digestive enzymes. The mineral content includes sodium, potassium, calcium, magnesium, sodium bicarbonate, potassium bicarbonate, and calcium carbonate.
The product also provides lipase, cellulase, pectinase, amylase, protease blend, and papain—enzymes intended to support digestion. Herbal ingredients are ginger, marshmallow, papaya, holy basil, and rosemary, supplied as extracts or powders in a proprietary herbal blend and a proprietary mineral blend.
The capsule itself is made from delayed-release vegetable material.
Does it work?
Not established
The evidence on file shows mixed support across the ingredients. Sodium is likely effective for cystic fibrosis and possibly effective for amphotericin B nephrotoxicity.
Calcium is effective for kidney failure, dyspepsia, and hypocalcemia, and likely effective for osteoporosis. Magnesium is effective for dyspepsia, constipation, and hypomagnesemia, and also for pre-eclampsia.
Ginger is possibly effective for pregnancy-induced nausea and vomiting and dysmenorrhea, and possibly osteoarthritis, though it was possibly ineffective for exercise-induced muscle soreness. The evidence for papaya and papain is rated insufficient; the same holds for holy basil and rosemary.
Marshmallow, lipase, and the enzyme blends have insufficient evidence for the conditions on file.
How safe is it?
Well-documented data
Sodium is generally well tolerated in normal dietary amounts, but too much is linked to high blood pressure and heart strain. Potassium from food is fine, but supplements can cause dangerously high blood levels in some people, especially those with kidney disease.
Calcium is generally well tolerated at recommended amounts; taking too much may raise concerns about kidney stones and possibly prostate cancer or heart disease, though the evidence is debated. Magnesium is generally well tolerated and may cause mild gastrointestinal effects like diarrhea or nausea at higher doses.
Ginger is generally well tolerated up to about 5 grams per day; higher doses increase side effects and reduce tolerability. Marshmallow is well tolerated for short-term use but has limited human safety data.
Papaya fruit is well tolerated as food; concentrated supplements and unripe papaya are less well studied. Holy basil seems well tolerated short-term but long-term safety data are limited.
Rosemary is safe in normal culinary amounts; concentrated extracts and undiluted essential oil require caution. Lipase, papain, and the enzyme blends may irritate the digestive tract in some people.
Sodium bicarbonate is generally well tolerated in small antacid doses but risky if overused or used long-term due to high sodium content.
Meds to double-check
Major interaction found
Before taking pH Balance, double-check with your doctor or pharmacist if you take any of the following: HIV integrase inhibitors (dolutegravir, elvitegravir, raltegravir), the antibiotic ceftriaxone, blood pressure drugs (especially ACE inhibitors, ARBs, or potassium-sparing diuretics), blood thinners (warfarin, phenprocoumon) or antiplatelet drugs, Parkinson's medication (levodopa/carbidopa), thyroid medication (levothyroxine), heart medications (calcium channel blockers, sotalol, diltiazem, amiodarone), diabetes drugs, quinolone antibiotics, bisphosphonates, or lithium. These carry the highest risks.
The bottom line
Scorecard at a glanceFormula with limited ingredient disclosure with no established evidence rating for its marketed use. Major medication interactions have been identified, and safety information is well characterized.
This is a multi-ingredient digestive and pH-support formula that brings together minerals, enzymes, and botanicals. Because it contains sodium, potassium, and calcium in meaningful amounts alongside magnesium and several herbal ingredients with known drug interactions, you'll want to check your medications carefully with the tool on this page—especially if you take blood pressure drugs, blood thinners, HIV medications, diabetes drugs, thyroid medication, or Parkinson's medication.
Talk with your doctor or pharmacist before adding this to your routine, particularly if you have kidney disease, heart disease, or are taking any prescription medications.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 15 of 19 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated May 22, 2021.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about pH Balance, straight from the product label.
| Brand | Theramedix BioSET |
|---|---|
| Barcode (UPC) | 738676953756 |
| Net contents | 90 Capsule(s) |
| Market status | On market |
| Date entered into DSLD | May 22, 2021 |
| DSLD ID | 247622 |
| Product type | Other Combinations |
| Supplement form | Capsule |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Vegetarian, Adult (18 - 50 Years) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for pH Balance by Theramedix BioSET, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Total Carbohydrates | 1 Gram(s) | 1% |
| Sodium | 6.5 mg | 1% |
| Potassium | 44.5 mg | 1.5% |
| Calcium | 16 mg | 2% |
| Magnesium | 1.6 mg | 1% |
| Lipase | 0 NP | -- |
| Cellulase | 0 NP | -- |
| Marshmallow | 0 NP | -- |
| Pectinase | 0 NP | -- |
| Ginger | 0 NP | -- |
| Magnesium Citrate | 0 NP | -- |
| Proprietary Herbal Blend | 325 mg | -- |
| Sodium Bicarbonate | 0 NP | -- |
| Potassium Bicarbonate | 0 NP | -- |
| Proprietary Enzyme Blend | 93 mg | -- |
| Proprietary Mineral Blend | 235 mg | -- |
| Papaya | 0 NP | -- |
| Holy Basil extract | 0 NP | -- |
| Rosemary | 0 NP | -- |
| Calcium Carbonate | 0 NP | -- |
| Amylase | 0 NP | -- |
| Protease Blend | 0 NP | -- |
| CereCalase | 0 NP | -- |
Other ingredients: delayed release vegetable Capsule
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formulation
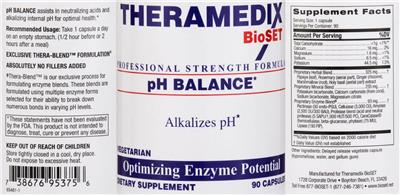
pH Balance assists in neutralizing acids and alkalizing internal pH for optimal health.
Professional strength formula
Alkalizes pH
Vegetarian
Optimizing enzyme potential
Suggested/Recommended/Usage/Directions
Recommended usage: Take 1 capsule a day on an empty stomach. (1/2 hour before or 2 hours after a meal)
Formula
Exclusive Thera-Blend formulation Thera-Blend is our exclusive process for formulating enzyme blends. These blends are formulated using multiple enzyme forms selected for their ability to break down numerous bonds in varying pH levels.
FDA Disclaimer Statement
These statements have not been evaluated by the FDA. This product is not intended to diagnose, treat, cure, or prevent any disease.
Precautions
Keep out of reach of children
Storage
Store tightly in a cool, dry place.
Do not expose to excessive heat.
FDA Statement of Identity
Dietary Supplement
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
pH Balance by Theramedix BioSET label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in pH Balance by Theramedix BioSET
These are the 19 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Capsule(s) Dosage formCapsule Servings per container90 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Sodium
Interacts with205 drugs
Sodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets g...
Sodium monograph & interactionsPotassium
Interacts with62 drugs
Potassium is an essential mineral your body needs for nerve signals, muscle function, and a steady heartbeat, and most people get enough from a balanc...
Potassium monograph & interactionsCalcium
Interacts with168 drugs
Calcium is an essential mineral your body needs for strong bones, nerve signaling, and muscle function, and supplements can help fill gaps when diet f...
Calcium monograph & interactionsMagnesium
Interacts with295 drugs
Magnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preven...
Magnesium monograph & interactionsProprietary Herbal Blend
- › Marshmallow
- › Ginger
- › Papaya
- › Holy Basil extract
- › Rosemary
Proprietary Enzyme Blend
- › Lipase
- › Cellulase
- › Pectinase
- › Amylase
- › Protease Blend
- › CereCalase
Proprietary Mineral Blend
Other (inactive) ingredients: Delayed release vegetable Capsule. These complete the product’s ingredient list but are not active constituents.
pH Balance by Theramedix BioSET Drug Interactions
HelloPharmacist Interaction Report
pH Balance by Theramedix BioSET interacts with medications through its sodium, potassium, calcium, magnesium, ginger, marshmallow, papaya, holy basil, rosemary, sodium bicarbonate, potassium bicarbonate, and papain (protease blend) content.
The most serious interaction is a Major-severity risk: calcium in this product can reduce blood levels of the HIV integrase inhibitors dolutegravir and elvitegravir by up to 40%, potentially compromising their effectiveness, and can also cause a dangerous precipitate when combined intravenously with the antibiotic ceftriaxone.
Read the full breakdown — every affected drug type, severity by severity
Moderate-severity interactions span several drug categories. Sodium can reduce the effectiveness of blood pressure medications (antihypertensives) and can dangerously raise sodium levels if you're also taking corticosteroids, the antiviral didanosine, sodium-containing drugs, or the diuretic tolvaptan; it also interferes with lithium levels.
Potassium supplements pose a serious risk of dangerously high blood potassium (hyperkalemia) with blood pressure drugs that preserve potassium—namely ACE inhibitors, ARBs, and potassium-sparing diuretics. Calcium can also reduce absorption of the thyroid drug levothyroxine and the heart medication sotalol; it may reduce levels of the HIV integrase inhibitor raltegravir, and theoretically may interact with calcipotriene and diltiazem.
Magnesium can sharply reduce levels of levodopa/carbidopa (a Parkinson's medication) by up to 35–81%, and can have additive blood-pressure-lowering effects with calcium channel blockers. It also decreases absorption of quinolone antibiotics, bisphosphonates, and may increase effects of diabetes medications and muscle relaxants.
Ginger may increase bleeding risk with anticoagulants (blood thinners) and antiplatelet drugs; it may increase blood-sugar-lowering effects of diabetes medications; it can alter levels of certain cancer drugs metabolized by CYP3A4; and it may increase levels of some heart and HIV medications. Marshmallow theoretically raises lithium levels and may impair absorption of oral medications.
Papaya may interact with diabetes drugs, warfarin, levothyroxine, and amiodarone. Holy basil may increase bleeding risk with anticoagulants and antiplatelet drugs and may increase blood-sugar-lowering effects.
Rosemary may increase bleeding risk with anticoagulants and antiplatelet drugs, may add to aspirin-like effects, and may interact with certain diabetes drugs. Sodium bicarbonate can reduce aspirin levels and may worsen potassium loss with diuretics and other drugs.
Papain (in the protease blend) theoretically increases warfarin effects.
Additionally, we could not check Cellulase, Pectinase, Amylase, and CereCalase—these ingredients have no interaction data on file. Altogether, these interactions span 2,185 individual medications.
Use the medication checker on this page to verify your exact drugs before starting.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against pH Balance?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in pH Balance interact with 2,184 drugs. Click any drug to see the details.
11 of the 19 ingredients in pH Balance interact with drugs. Each result below shows which ingredient is responsible. Marshmallow Ginger Rosemary Magnesium Sodium Bicarbonate Holy Basil extract Sodium Calcium Papaya Potassium Protease Blend
Benserazide, LevodopaMadopar, Prolopa
How Benserazide, Levodopa interacts with pH Balance — through 2 ingredients. Tap an ingredient for the detail:
Magnesium CitrateLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium Citrate + Benserazide, Levodopa interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Benserazide, Levodopa interactionCarbidopaLodosyn
How Carbidopa interacts with pH Balance — through 2 ingredients. Tap an ingredient for the detail:
Magnesium CitrateLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium Citrate + Carbidopa interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Carbidopa interactionCarbidopa, LevodopaDhivy, Rytary, Sinemet, Sinemet CR
How Carbidopa, Levodopa interacts with pH Balance — through 2 ingredients. Tap an ingredient for the detail:
Magnesium CitrateLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium Citrate + Carbidopa, Levodopa interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Carbidopa, Levodopa interactionCarbidopa, Levodopa, EntacaponeStalevo
How Carbidopa, Levodopa, Entacapone interacts with pH Balance — through 2 ingredients. Tap an ingredient for the detail:
Magnesium CitrateLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium Citrate + Carbidopa, Levodopa, Entacapone interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Carbidopa, Levodopa, Entacapone interactionCeftriaxoneRocephin
How Ceftriaxone interacts with pH Balance — through 1 ingredient. Tap an ingredient for the detail:
Calcium CarbonateCeftriaxone (rocephin) Major
Interaction Summary
Co-administration of intravenous calcium and ceftriaxone can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys.
Read the full Calcium Carbonate + Ceftriaxone interactionCobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide FumarateGenvoya
How Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interacts with pH Balance — through 4 ingredients. Tap an ingredient for the detail:
Calcium CarbonateElvitegravir (vitekta), Bictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Major
Interaction Summary
Calcium seems to reduce levels of elvitegravir.
Read the full Calcium Carbonate + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionMagnesium CitrateBictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Moderate
Interaction Summary
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Read the full Magnesium Citrate + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionGingerP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase the absorption and blood levels of P-glycoprotein (P-gp) substrates.
Read the full Ginger + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionDolutegravirTivicay
How Dolutegravir interacts with pH Balance — through 3 ingredients. Tap an ingredient for the detail:
Calcium CarbonateDolutegravir (tivicay) Major
Interaction Summary
Calcium seems to reduce levels of dolutegravir.
Read the full Calcium Carbonate + Dolutegravir interactionGingerP-glycoprotein Substrates Moderate
Interaction Summary
Ginger might increase the absorption and blood levels of P-glycoprotein (P-gp) substrates.
Read the full Ginger + Dolutegravir interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Dolutegravir interactionDolutegravir, Emtricitabine, Tenofovir AlafenamideDolutegravir, Emtricitabine, Tenofovir Alafenamide
How Dolutegravir, Emtricitabine, Tenofovir Alafenamide interacts with pH Balance — through 4 ingredients. Tap an ingredient for the detail:
Calcium CarbonateDolutegravir (tivicay), Bictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Major
Interaction Summary
Calcium seems to reduce levels of dolutegravir.
Read the full Calcium Carbonate + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionGingerP-glycoprotein Substrates Moderate
Interaction Summary
Ginger might increase the absorption and blood levels of P-glycoprotein (P-gp) substrates.
Read the full Ginger + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionMagnesium CitrateBictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Moderate
Interaction Summary
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Read the full Magnesium Citrate + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionDolutegravir, RilpivirineJuluca
How Dolutegravir, Rilpivirine interacts with pH Balance — through 3 ingredients. Tap an ingredient for the detail:
Calcium CarbonateDolutegravir (tivicay) Major
Interaction Summary
Calcium seems to reduce levels of dolutegravir.
Read the full Calcium Carbonate + Dolutegravir, Rilpivirine interactionGingerCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger + Dolutegravir, Rilpivirine interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Dolutegravir, Rilpivirine interactionElvitegravirVitekta
How Elvitegravir interacts with pH Balance — through 3 ingredients. Tap an ingredient for the detail:
Calcium CarbonateElvitegravir (vitekta) Major
Interaction Summary
Calcium seems to reduce levels of elvitegravir.
Read the full Calcium Carbonate + Elvitegravir interactionGingerCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger + Elvitegravir interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Elvitegravir interactionElvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil FumarateStribild
How Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interacts with pH Balance — through 4 ingredients. Tap an ingredient for the detail:
Calcium CarbonateElvitegravir (vitekta), Bictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Major
Interaction Summary
Calcium seems to reduce levels of elvitegravir.
Read the full Calcium Carbonate + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionGingerCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionMagnesium CitrateBictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Moderate
Interaction Summary
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Read the full Magnesium Citrate + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionLevodopaInbrija, Larodopa
How Levodopa interacts with pH Balance — through 2 ingredients. Tap an ingredient for the detail:
Magnesium CitrateLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium Citrate + Levodopa interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Levodopa interactionLevodopa, CarbidopaDuodopa
How Levodopa, Carbidopa interacts with pH Balance — through 1 ingredient. Tap an ingredient for the detail:
Magnesium CitrateLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium Citrate + Levodopa, Carbidopa interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with pH Balance — through 1 ingredient. Tap an ingredient for the detail:
GingerCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger + Ado-trastuzumab Emtansine interactionAbciximabReoPro
How Abciximab interacts with pH Balance — through 5 ingredients. Tap an ingredient for the detail:
GingerAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Ginger may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Ginger + Abciximab interactionRosemaryAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, rosemary may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Rosemary + Abciximab interactionHoly Basil ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, holy basil seed oil might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Holy Basil Extract + Abciximab interactionMarshmallowAnticoagulant/antiplatelet Drugs, Oral Drugs Minor
Interaction Summary
Theoretically, marshmallow flower might have antiplatelet effects.
Read the full Marshmallow + Abciximab interactionMagnesium CitrateAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium Citrate + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with pH Balance — through 2 ingredients. Tap an ingredient for the detail:
GingerCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger + Abemaciclib interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Abemaciclib interactionAbiraterone
How Abiraterone interacts with pH Balance — through 2 ingredients. Tap an ingredient for the detail:
GingerCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger + Abiraterone interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with pH Balance — through 2 ingredients. Tap an ingredient for the detail:
GingerCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger + Abiraterone Acetate interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with pH Balance — through 5 ingredients. Tap an ingredient for the detail:
GingerAnticoagulant/antiplatelet Drugs, Cytochrome P450 2c9 (cyp2c9) Substrates Moderate
Interaction Summary
Ginger may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Ginger + Abrocitinib interactionHoly Basil ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, holy basil seed oil might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Holy Basil Extract + Abrocitinib interactionRosemaryAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, rosemary may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Rosemary + Abrocitinib interactionMarshmallowOral Drugs, Anticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Abrocitinib interactionMagnesium CitrateAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium Citrate + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with pH Balance — through 2 ingredients. Tap an ingredient for the detail:
GingerCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger + Acalabrutinib interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with pH Balance — through 5 ingredients. Tap an ingredient for the detail:
GingerAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking ginger with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Ginger + Acarbose interactionRosemaryAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking rosemary with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Rosemary + Acarbose interactionPapayaAntidiabetes Drugs Moderate
Interaction Summary
Concomitant use of antidiabetic drugs with fermented papaya can produce additive effects.
Read the full Papaya + Acarbose interactionHoly Basil ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, holy basil might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Read the full Holy Basil Extract + Acarbose interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with pH Balance — through 2 ingredients. Tap an ingredient for the detail:
SodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Acebutolol interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with pH Balance — through 5 ingredients. Tap an ingredient for the detail:
RosemaryAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, rosemary may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Rosemary + Acenocoumarol interactionGingerAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Ginger may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Ginger + Acenocoumarol interactionHoly Basil ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, holy basil seed oil might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Holy Basil Extract + Acenocoumarol interactionMarshmallowOral Drugs, Anticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Acenocoumarol interactionMagnesium CitrateAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium Citrate + Acenocoumarol interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with pH Balance — through 6 ingredients. Tap an ingredient for the detail:
GingerAnticoagulant/antiplatelet Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Ginger may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Ginger + Acetaminophen, Aspirin interactionSodium BicarbonateAspirin Moderate
Interaction Summary
Theoretically, sodium bicarbonate may reduce the levels and clinical effects of aspirin.
Read the full Sodium Bicarbonate + Acetaminophen, Aspirin interactionHoly Basil ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, holy basil seed oil might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Holy Basil Extract + Acetaminophen, Aspirin interactionRosemaryCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary + Acetaminophen, Aspirin interactionMarshmallowAnticoagulant/antiplatelet Drugs, Oral Drugs Minor
Interaction Summary
Theoretically, marshmallow flower might have antiplatelet effects.
Read the full Marshmallow + Acetaminophen, Aspirin interactionMagnesium CitrateAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium Citrate + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with pH Balance — through 6 ingredients. Tap an ingredient for the detail:
RosemaryAspirin, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, rosemary might have additive effects with salicylate-containing drugs such as aspirin.
Read the full Rosemary + Acetaminophen, Aspirin, Caffeine interactionGingerAnticoagulant/antiplatelet Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Ginger may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Ginger + Acetaminophen, Aspirin, Caffeine interactionHoly Basil ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, holy basil seed oil might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Holy Basil Extract + Acetaminophen, Aspirin, Caffeine interactionSodium BicarbonateAspirin, Methylxanthines Moderate
Interaction Summary
Theoretically, sodium bicarbonate may reduce the levels and clinical effects of aspirin.
Read the full Sodium Bicarbonate + Acetaminophen, Aspirin, Caffeine interactionMarshmallowOral Drugs, Anticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Acetaminophen, Aspirin, Caffeine interactionMagnesium CitrateAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium Citrate + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with pH Balance — through 4 ingredients. Tap an ingredient for the detail:
GingerCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Ginger + Acetaminophen, Butalbital, Caffeine interactionSodium BicarbonateMethylxanthines Moderate
Interaction Summary
Theoretically, sodium bicarbonate may increase the risk of hypokalemia in patients taking methylxanthines.
Read the full Sodium Bicarbonate + Acetaminophen, Butalbital, Caffeine interactionRosemaryCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary + Acetaminophen, Butalbital, Caffeine interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with pH Balance — through 4 ingredients. Tap an ingredient for the detail:
Sodium BicarbonateMethylxanthines Moderate
Interaction Summary
Theoretically, sodium bicarbonate may increase the risk of hypokalemia in patients taking methylxanthines.
Read the full Sodium Bicarbonate + Acetaminophen, Butalbital, Caffeine, Codeine interactionGingerCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger + Acetaminophen, Butalbital, Caffeine, Codeine interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Acetaminophen, Butalbital, Caffeine, Codeine interactionRosemaryCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with pH Balance — through 4 ingredients. Tap an ingredient for the detail:
GingerCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionSodium BicarbonateMethylxanthines Moderate
Interaction Summary
Theoretically, sodium bicarbonate may increase the risk of hypokalemia in patients taking methylxanthines.
Read the full Sodium Bicarbonate + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionRosemaryCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with pH Balance — through 4 ingredients. Tap an ingredient for the detail:
GingerCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginger might increase the levels of CYP1A2 substrates.
Read the full Ginger + Acetaminophen, Caffeine, Codeine interactionSodium BicarbonateMethylxanthines Moderate
Interaction Summary
Theoretically, sodium bicarbonate may increase the risk of hypokalemia in patients taking methylxanthines.
Read the full Sodium Bicarbonate + Acetaminophen, Caffeine, Codeine interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Acetaminophen, Caffeine, Codeine interactionRosemaryCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with pH Balance — through 4 ingredients. Tap an ingredient for the detail:
GingerCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Ginger might increase or decrease the levels of CYP3A4 substrates.
Read the full Ginger + Acetaminophen, Caffeine, Codeine, Salicylamide interactionSodium BicarbonateMethylxanthines Moderate
Interaction Summary
Theoretically, sodium bicarbonate may increase the risk of hypokalemia in patients taking methylxanthines.
Read the full Sodium Bicarbonate + Acetaminophen, Caffeine, Codeine, Salicylamide interactionRosemaryCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary + Acetaminophen, Caffeine, Codeine, Salicylamide interactionMarshmallowOral Drugs Minor
Interaction Summary
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Read the full Marshmallow + Acetaminophen, Caffeine, Codeine, Salicylamide interactionEach ingredient & the kinds of drugs it affects
For each ingredient in pH Balance with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Marshmallow
Lithium
Theoretically, due to potential diuretic effects, marshmallow might reduce excretion and increase levels of lithium.
Marshmallow is thought to have diuretic properties. To avoid lithium toxicity, the dose of lithium might need to be decreased when used with marshmallow.
Anticoagulant/Antiplatelet Drugs
Theoretically, marshmallow flower might have antiplatelet effects.
Animal research suggests that marshmallow flower extract has antiplatelet effects. However, the root and leaf of marshmallow, not the flower, are the plant parts most commonly found in dietary supplements. Theoretically, use of marshmallow flower with anticoagulant/antiplatelet drugs can have additive effects, and might increase the risk for bleeding in some patients.
Oral Drugs
Theoretically, mucilage in marshmallow might impair absorption of oral drugs.
Marshmallow contains mucilage which can affect oral drug absorption. To avoid changes in absorption, take marshmallow 30-60 minutes after oral medications.
Ginger
Anticoagulant/Antiplatelet Drugs
Ginger may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs. However, research is conflicting.
Laboratory research suggests that ginger inhibits thromboxane synthetase and decreases platelet aggregation. However, this has not been demonstrated unequivocally in humans, with mixed results from clinical trials. Theoretically, excessive amounts of ginger might increase the risk of bleeding when used with anticoagulant/antiplatelet drugs.
Antidiabetes Drugs
Theoretically, taking ginger with antidiabetes drugs might increase the risk of hypoglycemia.
Animal and human research suggests that ginger might increase insulin levels and/or decrease blood glucose levels.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Ginger might increase or decrease the levels of CYP3A4 substrates.
In vitro research and some case reports suggest that ginger inhibits CYP3A4 activity. Three case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking ginger and cancer medications that are CYP3A4 substrates (imatinib, dabrafenib, and crizotinib). However, the causality of this interaction is unclear due to the presence of multiple interacting drugs and routes of administration.
Conversely, other in vitro research suggests that ginger induces CYP3A4 activity, leading to reduced levels of CYP3A4 substrates. However, this interaction has not been reported in humans.
Losartan (Cozaar)
Theoretically, ginger might increase levels of losartan and the risk of hypotension.
In animal research, ginger increased the levels and hypotensive effects of a single dose of losartan. It is not clear if ginger alters the concentration or effects of losartan when taken continuously. Additionally, this interaction has not been shown in humans.
Nifedipine (Procardia)
Ginger may have antiplatelet effects and increase the risk of bleeding if used with nifedipine.
Clinical research shows that combined treatment with ginger 1 gram plus nifedipine 10 mg significantly inhibits platelet aggregation when compared to nifedipine or ginger alone.
P-Glycoprotein Substrates
Ginger might increase the absorption and blood levels of P-glycoprotein (P-gp) substrates.
In vitro research and case reports suggest that ginger inhibits drug efflux by P-gp, potentially increasing absorption and serum levels of P-gp substrates. Two case reports from the World Health Organization (WHO) adverse drug reaction database describe increased toxicity in patients taking ginger and cancer medications that are P-gp substrates (trametinib, crizotinib). However, the causality of this interaction is unclear due to the presence of multiple interacting drugs and routes of administration.
Phenprocoumon (Marcoumar, Others)
Ginger might increase the risk of bleeding with phenprocoumon.
Phenprocoumon, a warfarin-related anticoagulant, might increase the international normalized ratio (INR) when taken with ginger. There is one case report of a 76-year-old woman with a stable INR on phenprocoumon that increased to greater than 10 when she began consuming dried ginger and ginger tea.
Warfarin (Coumadin)
Ginger might increase the risk of bleeding with warfarin.
Laboratory research suggests that ginger might inhibit thromboxane synthetase and decrease platelet aggregation. In one case report, ginger increased the INR when taken with phenprocoumon, which has similar pharmacological effects as warfarin. In another case report, ginger increased the INR when taken with a combination of warfarin, hydrochlorothiazide, and acetaminophen. A longitudinal analysis suggests that taking ginger increases the risk of bleeding in patients taking warfarin for at least 4 months. However, research in healthy people suggests that ginger has no effect on INR, or the pharmacokinetics or pharmacodynamics of warfarin. Until more is known, monitor INRs closely in patients taking large amounts of ginger.
Calcium Channel Blockers
Theoretically, taking ginger with calcium channel blockers might increase the risk of hypotension.
Some animal and in vitro research suggests that ginger has hypotensive and calcium channel-blocking effects. Another animal study shows that concomitant administration of ginger and the calcium channel blocker amlodipine leads to greater reductions in blood pressure when compared with amlodipine alone.
Cyclosporine (Neoral, Sandimmune)
Theoretically, when taken prior to cyclosporine, ginger might decrease cyclosporine levels.
In an animal model, ginger juice taken 2 hours prior to cyclosporine administration reduced the maximum concentration and area under the curve of cyclosporine by 51% and 40%, respectively. This effect was not observed when ginger juice and cyclosporine were administered at the same time.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, ginger might increase the levels of CYP1A2 substrates.
In vitro research shows that ginger inhibits CYP1A2 activity. However, this interaction has not been reported in humans.
Cytochrome P450 2B6 (Cyp2B6) Substrates
Theoretically, ginger might increase the levels of CYP2B6 substrates.
In vitro research shows that ginger inhibits CYP2B6 activity. However, this interaction has not been reported in humans.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, ginger might increase the levels of CYP2C9 substrates.
In vitro research shows that ginger inhibits CYP2C9 activity. However, this interaction has not been reported in humans.
Metronidazole (Flagyl)
Theoretically, ginger might increase levels of metronidazole.
In an animal model, ginger increased the absorption and plasma half-life of metronidazole. In addition, the elimination rate and clearance of metronidazole was significantly reduced.
Rosemary
Anticoagulant/Antiplatelet Drugs
Theoretically, rosemary may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro and animal research suggests that rosemary inhibits platelet aggregation.
Antidiabetes Drugs
Theoretically, taking rosemary with antidiabetes drugs might increase the risk of hypoglycemia.
Animal research shows that rosemary extract can decrease blood glucose levels in diabetic models. However, research in humans is conflicting. Although rosemary powder decreased blood glucose levels in healthy adults, no change in blood glucose levels was seen in adults with type 2 diabetes, most of whom were taking antidiabetes drugs.
Aspirin
Theoretically, rosemary might have additive effects with salicylate-containing drugs such as aspirin.
Rosemary is reported to contain salicylates.
Choline Magnesium Trisalicylate (Trilisate)
Theoretically, rosemary might have additive effects with salicylate-containing drugs such as choline magnesium trisalicylate.
Rosemary is reported to contain salicylate.
Salsalate (Disalcid)
Theoretically, rosemary might have additive effects with salicylate-containing drugs such as salsalate.
Rosemary is reported to contain salicylate.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
In vitro research shows that rosemary induces CYP1A2 enzymes. This effect has not been reported in humans.
Magnesium
Levodopa/Carbidopa (Sinemet)
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Clinical research in healthy volunteers shows that taking magnesium oxide 1000 mg with levodopa 100 mg/carbidopa 10 mg reduces the area under the curve (AUC) of levodopa by 35% and of carbidopa by 81%. In vitro and animal research shows that magnesium produces an alkaline environment in the digestive tract, which might lead to degradation and reduced bioavailability of levodopa/carbidopa.
Aminoglycoside Antibiotics
Concomitant use of aminoglycoside antibiotics and magnesium can increase the risk for neuromuscular weakness.
Both aminoglycosides and magnesium reduce presynaptic acetylcholine release, which can lead to neuromuscular blockade and possible paralysis. This is most likely to occur with high doses of magnesium given intravenously.
Antacids
Use of acid reducers may reduce the laxative effect of magnesium oxide.
A retrospective analysis shows that, in the presence of H2 receptor antagonists (H2RAs) or proton pump inhibitors (PPIs), a higher dose of magnesium oxide is needed for a laxative effect. This may also occur with antacids. Under acidic conditions, magnesium oxide is converted to magnesium chloride and then to magnesium bicarbonate, which has an osmotic laxative effect. By reducing acidity, antacids may reduce the conversion of magnesium oxide to the active bicarbonate salt.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after magnesium containing products.
Bisphosphonates
Magnesium can decrease absorption of bisphosphonates.
Cations, including magnesium, can decrease bisphosphonate absorption. Advise patients to separate doses of magnesium and these drugs by at least 2 hours.
Calcium Channel Blockers
Magnesium can have additive effects with calcium channel blockers, although evidence is conflicting.
Magnesium inhibits calcium entry into smooth muscle cells and may therefore have additive effects with calcium channel blockers. Severe hypotension and neuromuscular blockades may occur when nifedipine is used with intravenous magnesium, although some contradictory evidence suggests that concurrent use of magnesium with nifedipine does not increase the risk of neuromuscular weakness. High doses of magnesium could theoretically have additive effects with other calcium channel blockers.
Digoxin
Magnesium salts may reduce absorption of digoxin.
Clinical evidence suggests that treatment with oral magnesium hydroxide or magnesium trisilicate reduces absorption of digoxin from the intestines. This may reduce the blood levels of digoxin and decrease its therapeutic effects.
Potassium-Sparing Diuretics
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Potassium-sparing diuretics also have magnesium-sparing properties, which can counteract the magnesium losses associated with loop and thiazide diuretics. Theoretically, increased magnesium levels could result from concomitant use of potassium-sparing diuretics and magnesium supplements.
Quinolone Antibiotics
Magnesium decreases absorption of quinolones.
Magnesium can form insoluble complexes with quinolones and decrease their absorption. Advise patients to take these drugs at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Skeletal Muscle Relaxants
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Parenteral magnesium shortens the time to onset of skeletal muscle relaxants by about 1 minute and prolongs the duration of action by about 2 minutes. Magnesium potentiates the effects of skeletal muscle relaxants by decreasing calcium-mediated release of acetylcholine from presynaptic nerve terminals, reducing postsynaptic sensitivity to acetylcholine, and having a direct effect on the membrane potential of myocytes. Magnesium also has vasodilatory actions and increases cardiac output, allowing a greater amount of muscle relaxant to reach the motor end plate. A clinical study found that low-dose rocuronium (0.45 mg/kg), when given after administration of magnesium 30 mg/kg over 10 minutes, has an accelerated onset of effect, which matches the onset of effect seen with a full-dose rocuronium regimen (0.6 mg/kg). In another clinical study, onset times for rocuronium doses of 0.3, 0.6, and 1.2 mg/kg were 86, 76, and 50 seconds, respectively, when given alone, but were reduced to 66, 44, and 38 seconds, respectively, when the doses were given after a 15-minute infusion of magnesium sulfate 60 mg/kg. Giving intraoperative intravenous magnesium sulfate, 50 mg/kg loading dose followed by 15 mg/kg/hour, reduces the onset time of rocuronium, enhances its clinical effects, reduces the dose of intraoperative opiates, and prolongs the spontaneous recovery time. It does not affect the activity of subsequently administered neostigmine.
Sulfonylureas
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Clinical research shows that administration of magnesium hydroxide with glyburide increases glyburide absorption, increases maximal insulin response by 35-fold, and increases the risk of hypoglycemia, when compared with glyburide alone. A similar interaction occurs between magnesium hydroxide and glipizide. The mechanism of this effect appears to be related to the elevation of gastrointestinal pH by magnesium-based antacids, increasing solubility and enhancing absorption of sulfonylureas.
Tetracycline Antibiotics
Magnesium decreases absorption of tetracyclines.
Magnesium can form insoluble complexes with tetracyclines in the gut and decrease their absorption and antibacterial activity. Advise patients to take these drugs 1 hour before or 2 hours after magnesium supplements.
Anticoagulant/Antiplatelet Drugs
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
In vitro evidence shows that magnesium sulfate inhibits platelet aggregation, even at low concentrations. Some preliminary clinical evidence shows that infusion of magnesium sulfate increases bleeding time by 48% and reduces platelet activity. However, other clinical research shows that magnesium does not affect platelet aggregation, although inhibition of platelet-dependent thrombosis can occur.
Gabapentin (Neurontin)
Gabapentin absorption can be decreased by magnesium.
Clinical research shows that giving magnesium oxide orally along with gabapentin decreases the maximum plasma concentration of gabapentin by 33%, time to maximum concentration by 36%, and area under the curve by 43%. Advise patients to take gabapentin at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Sevelamer (Renagel, Renvela)
Sevelamer may increase serum magnesium levels.
In patients on hemodialysis, sevelamer use was associated with a 0.28 mg/dL increase in serum magnesium. The mechanism of this interaction remains unclear.
Sodium Bicarbonate
Aminoglycoside Antibiotics
Theoretically, sodium bicarbonate may increase the risk for hypokalemia in patients receiving aminoglycosides.
Orally, use of excessive sodium bicarbonate (such as the intake of "tablespoons" of sodium bicarbonate daily or up to one box of baking soda weekly) has been associated with cases of hypokalemia. Furthermore, when administered intravenously, the most common complication of sodium bicarbonate is hypokalemia. Nephrotoxicity caused by aminoglycosides may lead to increased urinary losses of various electrolytes, including potassium.
Amphotericin-B (Abelcet, Others)
Theoretically, sodium bicarbonate may increase the risk for hypokalemia in patients receiving amphotericin B.
Orally, use of excessive sodium bicarbonate (such as the intake of "tablespoons" of sodium bicarbonate daily or up to one box of baking soda weekly) has been associated with cases of hypokalemia. Furthermore, when administered intravenously, the most common complication of sodium bicarbonate is hypokalemia. Amphotericin B increases urinary potassium losses due to toxic effects on renal tubular epithelium. Hypokalemia can occur in up to 50% of patients.
Aspirin
Theoretically, sodium bicarbonate may reduce the levels and clinical effects of aspirin.
In humans, oral or intravenous administration of sodium bicarbonate increases salicylate elimination. Although the exact mechanism of this effect is not clear, some researchers hypothesize that sodium bicarbonate increases urinary pH, which increases salicylate ionization and subsequent excretion by the kidneys. In patients with urine pH of about 5.5, renal clearance of salicylate is approximately 55 mL/min. When urine pH is increased with oral sodium bicarbonate to about 7.5, renal clearance of salicylate increases to approximately 100 mL/min. Similarly, urine alkalinization with sodium bicarbonate increases the mean total body clearance of salicylate by approximately 60% compared with urine acidification.
Beta-Adrenergic Agonists
Theoretically, sodium bicarbonate may increase the risk for hypokalemia in patients taking beta-adrenergic agonists.
Orally, use of excessive sodium bicarbonate (such as the intake of "tablespoons" of sodium bicarbonate daily or up to one box of baking soda weekly) has been associated with cases of hypokalemia. Furthermore, the most common adverse effect of intravenous sodium bicarbonate is hypokalemia. Oral, parenteral, or inhaled beta-adrenergic agonists can reduce serum potassium levels, especially during acute use of high doses.
Cefpodoxime Proxetil (Vantin)
Theoretically, sodium bicarbonate might reduce the levels and clinical effects of cefpodoxime.
Cefpodoxime proxetil is an oral prodrug that is de-esterified in the intestine to the active drug cefpodoxime. Drugs or supplements that increase gastric pH can inhibit the activation of cefpodoxime proxetil and reduce the peak plasma concentrations of cefpodoxime. In humans, taking sodium bicarbonate 12.6 grams orally along with cefpodoxime proxetil 200 mg reduces peak plasma concentrations and area under the plasma concentration-time curve (AUC) of cefpodoxime by 35% to 50%.
Chlorpropamide (Diabinese)
Theoretically, sodium bicarbonate might reduce the levels and clinical effects of chlorpropamide.
The elimination of chlorpropamide by the kidneys depends strongly on urine pH. At a pH of 5, the renal clearance of chlorpropamide ranges from 0.5 to 3 mL/hr. At a pH of 8, renal clearance of chlorpropamide ranges from 500 to 1000 mL/hr. When taken in combination with oral sodium bicarbonate, the elimination half-life of chlorpropamide is shortened from 49.7 to 12.8 hours and urinary excretion of chlorpropamide is increased four-fold.
Cisplatin (Platinol-Aq)
Theoretically, sodium bicarbonate may increase the risk of hypokalemia in patients receiving cisplatin.
Orally, use of excessive sodium bicarbonate (such as the intake of "tablespoons" of sodium bicarbonate daily or up to one box of baking soda weekly) has been associated with cases of hypokalemia. Furthermore, the most common complication of intravenous sodium bicarbonate is hypokalemia. Cisplatin can cause renal tubular damage, with increased losses of electrolytes including potassium.
Corticosteroids
Theoretically, sodium bicarbonate may increase the risk of hypokalemia in patients taking corticosteroids.
Orally, use of excessive sodium bicarbonate (such as the intake of "tablespoons" of sodium bicarbonate daily or up to one box of baking soda weekly) has been associated with cases of hypokalemia. Furthermore, the most common intravenous complication of sodium bicarbonate is hypokalemia. Some glucocorticoids (corticosteroids) can also cause hypokalemia by causing sodium retention, resulting in compensatory renal potassium excretion. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Loop Diuretics
Theoretically, sodium bicarbonate may increase the risk of hypokalemia in patients taking loop diuretics.
Loop diuretics increase urinary potassium excretion. Orally, use of excessive sodium bicarbonate (such as the intake of "tablespoons" of sodium bicarbonate daily or up to one box of baking soda weekly) has been associated with cases of hypokalemia. Furthermore, the most common complication of intravenous sodium bicarbonate is hypokalemia.
Methylxanthines
Theoretically, sodium bicarbonate may increase the risk of hypokalemia in patients taking methylxanthines.
Orally, use of excessive sodium bicarbonate (such as the intake of "tablespoons" of sodium bicarbonate daily or up to one box of baking soda weekly) has been associated with cases of hypokalemia. Furthermore, the most common complication of intravenous sodium bicarbonate is hypokalemia. Theophylline and related drugs can reduce serum potassium levels, possibly by increasing intracellular uptake of potassium. Hypokalemia is most likely to occur after acute overdose of these drugs. However, reduced potassium levels can occur with therapeutic doses, and the incidence and degree of hypokalemia increases with increasing serum theophylline levels.
Pseudoephedrine (Sudafed)
Theoretically, sodium bicarbonate may increase levels and adverse effects of pseudoephedrine.
In humans, intravenous or oral administration of sodium bicarbonate can increase urinary pH. Clinical evidence shows that urine alkalinization increases the serum elimination half-life of pseudoephedrine by approximately 10-fold. In one patient with persistently alkaline urine, treatment with pseudoephedrine resulted in hallucinations and personality changes.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related adverse effects.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium bicarbonate, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Stimulant Laxatives
Theoretically, sodium bicarbonate may increase the risk of hypokalemia in patients taking stimulant laxatives.
Long-term use of stimulant laxatives, or acute use of high doses (e.g., in bowel-cleansing regimens), can result in potassium loss and hypokalemia. Orally, use of excessive sodium bicarbonate (such as intake of "tablespoons" of sodium bicarbonate daily or up to one box of baking soda weekly) has been associated with cases of hypokalemia. Furthermore, the most common complication of intravenous sodium bicarbonate is hypokalemia.
Thiazide Diuretics
Theoretically, sodium bicarbonate may increase the risk of hypokalemia in patients taking thiazide diuretics.
Thiazide diuretics increase urinary potassium excretion. Orally, use of excessive sodium bicarbonate (such as the intake of "tablespoons" of sodium bicarbonate daily or up to one box of baking soda weekly) has been associated with cases of hypokalemia. Furthermore, the most common complication of intravenous sodium bicarbonate is hypokalemia.
Holy Basil extract
Anticoagulant/Antiplatelet Drugs
Theoretically, holy basil seed oil might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Animal research shows that holy basil seed oil can prolong bleeding time, possibly due to inhibition of platelet aggregation. However, it is not known if this occurs in humans.
Antidiabetes Drugs
Theoretically, holy basil might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Small clinical studies show that taking holy basil can decrease fasting blood glucose and other measures of glycemic control in patients with type 2 diabetes.
Pentobarbital (Nembutal)
Theoretically, holy basil seed oil might increase the sedative effects of pentobarbital.
Animal research shows that holy basil seed oil increases pentobarbitone-induced sleeping time. However, it is not known if this occurs in humans or if this applies to other barbiturates or sedatives.
Sodium
Antihypertensive Drugs
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
High intake of dietary sodium can increase systolic and diastolic blood pressure. Also, high intake of sodium may necessitate increased use of antihypertensive medications to achieve blood pressure control in some patients, such as those with chronic kidney disease.
Corticosteroids
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Mineralocorticoids and some glucocorticoids (corticosteroids) cause sodium retention. This effect is dose-related and depends on mineralocorticoid potency. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Didanosine (Videx)
Concomitant use of didanosine with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia.
Didanosine formulations contain a significant amount of sodium.
Lithium
Altering dietary intake of sodium might alter the levels and clinical effects of lithium.
High sodium intake can reduce plasma concentrations of lithium by increasing lithium excretion. Reducing sodium intake can significantly increase plasma concentrations of lithium and cause lithium toxicity in patients being treated with lithium carbonate. Stabilizing sodium intake is shown to reduce the percentage of patients with lithium level fluctuations above 0.8 mEq/L. Patients taking lithium should avoid significant alterations in their dietary intake of sodium.
Sodium Phosphates
Theoretically, concomitant use of sodium phosphate with sodium supplements might increase the risk of hypernatremia.
Use of high doses (> 45 mL in 24 hours) of sodium phosphate, such as those used for bowel cleansing before surgery, can lead to serious electrolyte disturbances, including hypernatremia. The risk of hypernatremia is highest in the elderly and people with other risk factors for electrolyte disturbances.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related complications.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium supplements or high-sodium diets, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Tolvaptan (Samsca)
Theoretically, concomitant use of tolvaptan with sodium might increase the risk of hypernatremia.
Tolvaptan is a vasopressin receptor 2 antagonist that is used to increase sodium levels in patients with hyponatremia. Patients taking tolvaptan should use caution with the use of sodium salts such as sodium chloride.
Calcium
Ceftriaxone (Rocephin)
Co-administration of intravenous calcium and ceftriaxone can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys.
Avoid administering intravenous calcium in any form, such as parenteral nutrition or Lactated Ringers, within 48 hours of intravenous ceftriaxone. Case reports in neonates show that administering intravenous ceftriaxone and calcium can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys. In several cases, neonates have died as a result of this interaction. So far there are no reports in adults; however, there is still concern that this interaction might occur in adults.
Dolutegravir (Tivicay)
Calcium seems to reduce levels of dolutegravir.
Advise patients to take dolutegravir either 2 hours before or 6 hours after taking calcium supplements. Pharmacokinetic research suggests that taking calcium carbonate 1200 mg concomitantly with dolutegravir 50 mg reduces plasma levels of dolutegravir by almost 40%. Calcium appears to decrease levels of dolutegravir through chelation.
Elvitegravir (Vitekta)
Calcium seems to reduce levels of elvitegravir.
Advise patients to take elvitegravir either 2 hours before or 2 hours after taking calcium supplements. Pharmacokinetic research suggests that taking calcium along with elvitegravir can reduce blood levels of elvitegravir through chelation.
Aluminum
Calcium citrate might increase aluminum absorption and toxicity. Other types of calcium do not increase aluminum absorption.
Calcium citrate can increase the absorption of aluminum when taken with aluminum hydroxide. The increase in aluminum levels may become toxic, particularly in individuals with kidney disease. However, the effect of calcium citrate on aluminum absorption is due to the citrate anion rather than calcium cation. Calcium acetate does not appear to increase aluminum absorption.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Calcium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide and calcium can be taken together if taken with food. However, if taken on an empty stomach, bictegravir/emtricitabine/tenofovir alafenamide should not be taken with, or 2 hours after, calcium containing products.
Bisphosphonates
Calcium reduces the absorption of bisphosphonates.
Advise patients to take bisphosphonates at least 30 minutes before calcium, but preferably at a different time of day. Calcium supplements decrease absorption of bisphosphonates.
Calcipotriene (Dovonex)
Taking calcipotriene with calcium might increase the risk for hypercalcemia.
Calcipotriene is a vitamin D analog used topically for psoriasis. It can be absorbed in sufficient amounts to cause systemic effects, including hypercalcemia. Theoretically, combining calcipotriene with calcium supplements might increase the risk of hypercalcemia.
Digoxin (Lanoxin)
Using intravenous calcium with digoxin might increase the risk of fatal cardiac arrhythmias.
Hypercalcemia increases the risk of fatal cardiac arrhythmias with digoxin. However, one retrospective analysis of clinical data suggests that intravenous calcium does not increase the risk of dysrhythmias or mortality in patients receiving digoxin.
Diltiazem (Cardizem, Others)
Theoretically, calcium may reduce the therapeutic effects of diltiazem.
Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically, calcium might increase this risk of hypercalcemia and reduce the effectiveness of diltiazem.
Levothyroxine (Synthroid, Others)
Calcium seems to reduce the absorption and effectiveness of levothyroxine.
Advise patients to take levothyroxine and calcium supplements at least 4 hours apart. Calcium reduces levothyroxine absorption, probably by forming insoluble complexes. Calcium carbonate supplements reduce effectiveness of levothyroxine in patients with hypothyroidism.
Lithium
Theoretically, concomitant use of calcium and lithium may increase this risk of hypercalcemia.
Clinical research suggests that long-term use of lithium may cause hypercalcemia in 10% to 60% of patients. Theoretically, concomitant use of lithium and calcium supplements may further increase this risk.
Quinolone Antibiotics
Calcium seems to reduce the absorption of quinolone antibiotics.
Advise patients to take oral quinolones at least 2 hours before or 4-6 hours after calcium supplements or calcium-fortified foods. Taking calcium at the same time as oral quinolones can reduce quinolone absorption. Calcium binds to quinolones in the gut.
Raltegravir (Isentress)
Calcium may reduce levels of raltegravir.
Pharmacokinetic research shows that taking a single dose of calcium carbonate 3000 mg along with raltegravir 400 mg twice daily modestly decreases the mean area under the curve of raltegravir, but the decrease does not necessitate a dose adjustment of raltegravir. However, a case of elevated HIV-1 RNA levels and documented resistance to raltegravir has been reported for a patient taking calcium carbonate 1 gram three times daily plus vitamin D3 (cholecalciferol) 400 IU three times daily in combination with raltegravir 400 mg twice daily for 11 months. It is thought that calcium reduced raltegravir levels by chelation, leading to treatment failure.
Sotalol (Betapace)
Calcium seems to reduce the absorption of sotalol.
Advise patients to separate doses by at least 2 hours before or 4-6 hours after calcium. Calcium appears to reduce the absorption of sotalol, probably by forming insoluble complexes.
Tetracycline Antibiotics
Calcium seems to reduce the absorption of tetracycline antibiotics.
Advise patients to take oral tetracyclines at least 2 hours before, or 4-6 hours after calcium supplements. Taking calcium at the same time as oral tetracyclines can reduce tetracycline absorption. Calcium binds to tetracyclines in the gut.
Thiazide Diuretics
Taking calcium along with thiazides might increase the risk of hypercalcemia and renal failure.
Thiazides reduce calcium excretion by the kidneys. Using thiazides along with moderately large amounts of calcium carbonate increases the risk of milk-alkali syndrome (hypercalcemia, metabolic alkalosis, renal failure). Patients may need to have their serum calcium levels and/or parathyroid function monitored regularly.
Verapamil (Calan, Others)
Theoretically, calcium may reduce the therapeutic effects of verapamil.
Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically, use of calcium supplements may increase this risk of hypercalcemia and reduce the effectiveness of verapamil.
Calcium Channel Blockers
Intravenous calcium may decrease the effects of calcium channel blockers; oral calcium is unlikely to have this effect.
Intravenous calcium is used to decrease the effects of calcium channel blockers in the management of overdose. Intravenous calcium gluconate has been used before intravenous verapamil (Isoptin) to prevent or reduce the hypotensive effects without affecting the antiarrhythmic effects. But there is no evidence that dietary or supplemental calcium when taken orally interacts with calcium channel blockers.
Papaya
Amiodarone (Cordarone)
Theoretically, papaya extract may increase the levels and clinical effects of amiodarone.
Animal research in rats shows that a single oral dose of papaya extract, as well as multiple doses of papaya extract daily over 14 days, prior to a single dose of amiodarone delays the time to maximum amiodarone concentration. However, only the 14-day papaya extract regimen increases systemic amiodarone exposure by 60% to 70%. This interaction has not been reported in humans.
Antidiabetes Drugs
Concomitant use of antidiabetic drugs with fermented papaya can produce additive effects. It is unclear if other forms of papaya have the same effect.
A small low-quality clinical study in patients with type 2 diabetes who are taking glibenclamide shows that taking a fermented papaya preparation 3 grams daily for 2 months decreases fasting and postprandial blood glucose levels when compared to baseline. Additionally, of the 25 patients in the study, 9 required a reduction in glibenclamide dose.
Levothyroxine (Synthroid, Others)
Theoretically, consuming large quantities of papaya fruit can reduce the clinical effects of levothyroxine.
In one case-report, a 37-year-old male with a history of thyroidectomy who was stabilized on levothyroxine for 5 years presented with hypothyroidism after consuming 5-6 papaya fruits daily for 14 days during vacation. In a controlled re-challenge test involving 5-6 papayas daily, the patient remained euthyroid for 7 days, but developed mild hypothyroidism after 14 days. Both times, thyroid levels normalized 40-45 days after discontinuing papaya.
Warfarin (Coumadin)
Theoretically, concomitant use of warfarin with papain-containing papaya extract might increase the effects and side effects of warfarin.
In one case report, a patient previously stable on warfarin was found to have an international normalization ratio (INR) of 7.4, which was attributed to ingestion of a supplement containing papain from papaya extract.
Potassium
Ace Inhibitors (Aceis)
Using ACEIs with high doses of potassium increases the risk of hyperkalemia.
ACEIs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Angiotensin Receptor Blockers (Arbs)
Using ARBs with high doses of potassium increases the risk of hyperkalemia.
ARBs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Potassium-Sparing Diuretics
Concomitant use increases the risk of hyperkalemia.
Using potassium-sparing diuretics with potassium supplements increases the risk of hyperkalemia.
Protease Blend
Warfarin (Coumadin)
Theoretically, papain might increase the effects and side effects of warfarin.
In one case report, a patient previously stable on warfarin was found to have an international normalization ratio (INR) of 7.4, which was attributed to ingestion of a supplement containing papain from papaya extract.
Brand information
Manufacturer and brand details for pH Balance, from the product label.
Theramedix BioSET
See all Theramedix BioSET products- Name
- Theramedix BioSET
- Street Address
- 1728 Corporate Drive
- City
- Boynton Beach
- State
- FL
- ZipCode
- 33426
- Phone Number
- 877-246-7381
- Web Address
- www.bioset.net
pH Balance by Theramedix BioSET: Common Questions
Does pH Balance by Theramedix BioSET interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take pH Balance if I'm pregnant?
What side effects might I experience from pH Balance?
Is there enough evidence that pH Balance actually works?
Can I take pH Balance while breastfeeding?
What are the enzymes in this product supposed to do?
Why does pH Balance have both sodium and potassium?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if pH Balance is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind pH Balance’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Sodium
Interacts with 205 drugsSodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets get more than enough—often too much—from...
Read the full Sodium monograph → Herb & supplement monographPotassium
Interacts with 62 drugsPotassium is an essential mineral your body needs for nerve signals, muscle function, and a steady heartbeat, and most people get enough from a balanced diet rich in fruits and vegetables. P...
Read the full Potassium monograph → Herb & supplement monographCalcium
Interacts with 168 drugsCalcium is an essential mineral your body needs for strong bones, nerve signaling, and muscle function, and supplements can help fill gaps when diet falls short. Most people do best getting...
Read the full Calcium monograph → Herb & supplement monographMagnesium
Interacts with 295 drugsMagnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preventing or correcting deficiency. Some othe...
Read the full Magnesium monograph → Herb & supplement monographMarshmallow
Interacts with 2,040 drugsMarshmallow root is a traditional herb rich in soothing, gel-like fibers called mucilage, which is why it has long been used for coughs, sore throats, and stomach irritation. Evidence for th...
Read the full Marshmallow monograph → Herb & supplement monographGinger
Interacts with 1,007 drugsGinger is a widely used culinary spice with a long history in traditional medicine, and it has the strongest evidence for helping with nausea and vomiting, including from motion sickness, pr...
Read the full Ginger monograph → Herb & supplement monographPapaya
Interacts with 92 drugsPapaya is a tropical fruit that is nutritious and generally safe to eat as food, and it contains an enzyme called papain used as a digestive aid and meat tenderizer. Papaya leaf extract is b...
Read the full Papaya monograph → Herb & supplement monographHoly Basil
Interacts with 212 drugsHoly basil (tulsi) is a traditional Ayurvedic herb most often used today for stress and general wellness, but the human evidence is mostly small and preliminary. It is generally well tolerat...
Read the full Holy Basil monograph → Herb & supplement monographRosemary
Interacts with 372 drugsRosemary is a fragrant Mediterranean herb that is safe and flavorful in normal food amounts. Some early research suggests possible benefits for memory, mood, and hair growth, but the evidenc...
Read the full Rosemary monograph → Herb & supplement monographLipase
Lipase is a digestive enzyme that helps your body break down dietary fats. It is well established as part of prescription pancreatic enzyme therapy for people who cannot make enough of their...
Read the full Lipase monograph → Herb & supplement monographPapain
Interacts with 2 drugsPapain is a protein-digesting enzyme from the papaya plant that is used in digestive supplements and some topical products. While it has clear food and laboratory uses, strong human evidence...
Read the full Papain monograph → Herb & supplement monographSodium Bicarbonate
Interacts with 257 drugsSodium bicarbonate (baking soda) is a simple compound most often used as a fast-acting antacid and, in sports, as a buffer that may help with short, high-intensity exercise. It is generally...
Read the full Sodium Bicarbonate monograph →Sources & How We Checked
pH Balance's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 366 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Sodium 38 references
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Food and Drug Administration Science Background: Safety of Sodium Phosphates Oral Solution. September 17, 2001. Available at: http://www.fda.gov/cder/drug/safety/sodiumphospate.htm
- Coton T, Mallaret C, Coilliot C, Carre D, Guisset M. Severe acute ulcerated gastritis induced by salt. Presse Med 2009;38(3):499-500. PubMed
- Frings-Meuthen P, Buehlmeier J, Baecker N, et al. High sodium chloride intake exacerbates immobilization-induced bone resorption and protein losses. J Appl Physiol 2011;111(2):537-542. PubMed
- Frings-Meuthen P, Baecker N, Heer M. Low-grade metabolic acidosis may be the cause of sodium chloride-induced exaggerated bone resorption. J Bone Miner Res 2008;23(4):517-524. PubMed
- Alam S, Johnson AG. A meta-analysis of randomised controlled trials (RCT) among healthy normotensive and essential hypertensive elderly patients to determine the effect of high salt (NaCl) diet of blood pressure. J Hum Hypertens 1999;13(6):367-74.
- Boudville N, Ward S, Benaroia M, House AA. Increased sodium intake correlates with greater use of antihypertensive agents by subjects with chronic kidney disease. Am J Hypertens 2005;18(10):1300-5. PubMed
- Bennett WM. Drug interactions and consequences of sodium restriction. Am J Clin Nutr 1997;65(2 Suppl):678S-681S. PubMed
- Okusa MD, Crystal LJ. Clinical manifestations and management of acute lithium intoxication. Am J Med 1994;97(4):383-9. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary reference intakes for water, potassium, sodium, chloride, and sulfate. Washington, DC: National Academy Press, 2005. Available at: http://www.nap.edu/openbook.php?record_id=10925. DOI
- D'Elia L, Rossi G, Ippolito R, Cappuccio FP, Strazzullo P. Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clin Nutr 2012;31(4):489-98. PubMed
- Goldsmith SR. Hyponatremia in heart failure: time for a trial. J Card Fail 2013;19(6):398-400. PubMed
- Willocks L, Brettle R, Keen J, Valentine C, Pinching AJ. Formulations of didanosine (ddI) and salt overload. Lancet 1992;339(8786):190.
- Chen L, Zhang Z, Chen W, Whelton PK, Appel LJ. Lower Sodium Intake and Risk of Headaches: Results From the Trial of Nonpharmacologic Interventions in the Elderly. Am J Public Health. 2016;106(7):1270-5. PubMed
- Cook NR, Appel LJ, Whelton PK. Lower levels of sodium intake and reduced cardiovascular risk. Circulation. 2014;129(9):981-9. PubMed
- Cook NR, Appel LJ, Whelton PK. Sodium Intake and All-Cause Mortality Over 20 Years in the Trials of Hypertension Prevention. J Am Coll Cardiol. 2016;68(15):1609-1617. PubMed
- Mente A, O'Donnell M, Rangarajan S, et al. Associations of urinary sodium excretion with cardiovascular events in individuals with and without hypertension: a pooled analysis of data from four studies. Lancet. 2016;388(10043):465-75. PubMed
- Moosavian SP, Haghighatdoost F, Surkan PJ, Azadbakht L. Salt and obesity: a systematic review and meta-analysis of observational studies. Int J Food Sci Nutr. 2017;68(3):265-277. PubMed
- O'Donnell M, Mente A, Rangarajan S, et al. Urinary sodium and potassium excretion, mortality, and cardiovascular events. N Engl J Med. 2014;371(7):612-23. DOI
- Poggio R, Gutierrez L, Matta MG, Elorriaga N, Irazola V, Rubinstein A. Daily sodium consumption and CVD mortality in the general population: systematic review and meta-analysis of prospective studies. Public Health Nutr. 2015;18(4):695-704. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Mahtani KR, Heneghan C, Onakpoya I, et al. Reduced Salt Intake for Heart Failure: A Systematic Review. JAMA Intern Med. 2018 Dec 1;178(12):1693-1700. PubMed
- Yancy CW. Sodium Restriction in Heart Failure: Too Much Uncertainty-Do the Trials. JAMA Intern Med. 2018 Dec 1;178(12):1700-1701. PubMed
- He FJ, Campbell NRC, Ma Y, MacGregor GA, Cogswell ME, Cook NR. Errors in estimating usual sodium intake by the Kawasaki formula alter its relationship with mortality: implications for public health. Int J Epidemiol. 2018;47(6):1784-1795. PubMed
- Murthy K, Ondrey GJ, Malkani N, et al. THE EFFECTS OF HYPONATREMIA ON BONE DENSITY AND FRACTURES: A SYSTEMATIC REVIEW AND META-ANALYSIS. Endocr Pract. 2019;25(4):366-378. PubMed
- Messerli FH, Hofstetter L, Syrogiannouli L, et al. Sodium intake, life expectancy, and all-cause mortality. Eur Heart J 2021;42(21):2103-2112. PubMed
- Graudal NA, Hubeck-Graudal T, Jurgens G. Effects of low sodium diet versus high sodium diet on blood pressure, renin, aldosterone, catecholamines, cholesterol, and triglyceride. Cochrane Database Syst Rev 2020;12(12):CD004022. PubMed
- Giatti S, Santos RB, Aielo AN, et al. Association of sodium with obstructive sleep apnea. The ELSA-Brasil study. Ann Am Thorac Soc 2021;18(3):502-510. PubMed
- Nan X, Lu H, Wu J, et al. The interactive association between sodium intake, alcohol consumption and hypertension among elderly in northern China: a cross-sectional study. BMC Geriatr 2021;21(1):135. PubMed
- Kyozuka H, Fukusda T, Murata T, et al. Impact of preconception sodium intake on hypertensive disorders of pregnancy: The Japan Environment and Children's study. Pregnancy Hypertens 2021;23:66-72. PubMed
- Zhao L, Ogden CL, Yang Q, et al. Association of usual sodium intake with obesity among US children and adolescents, NHANES 2009-2016. Obesity (Silver Spring) 2021;29(3):587-594. PubMed
- Ma Y, He FJ, Sun Q, et al. 24-Hour urinary sodium and potassium excretion and cardiovascular risk. N Engl J Med 2022;386(3):252-263. PubMed
- Liu J, Yang X, Zhang P, et al. Association of urinary sodium excretion and left ventricular hypertrophy in people with type 2 diabetes mellitus: A cross-sectional study. Front Endocrinol (Lausanne) 2021;12:728493. PubMed
- Filippini T, Malavolti M, Whelton PK, Vinceti M. Sodium intake and risk of hypertension: A systematic review and dose-response meta-analysis of observational cohort studies. Curr Hypertens Rep 2022;24(5):133-144. PubMed
- Wang DD, Li Y, Nguyen XT, et al. Dietary sodium and potassium intake and risk of non-fatal cardiovascular diseases: The million veteran program. Nutrients 2022;14(5):1121. PubMed
- Kwak JH, Park CH, Eun CS, et al. The associations of dietary intake of high sodium and low zinc with gastric cancer mortality: A prospective cohort study in Korea. Nutr Cancer 2022;74(10):3501-3508. PubMed
- George S, Maiti R, Mishra BR, Jena M, Mohapatra D. Effect of regulated add-on sodium chloride intake on stabilization of serum lithium concentration in bipolar disorder: A randomized controlled trial. Bipolar Disord 2023;25(1):66-75. PubMed
- Zhou TL, Schütten MTJ, Kroon AA, et al. Urinary Sodium Excretion and Salt Intake Are Not Associated With Blood Pressure Variability in a White General Population. J Am Heart Assoc 2023;12(1):e026578. PubMed
Potassium 12 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Gennaro A. Remington: The Science and Practice of Pharmacy. 19th ed. Lippincott: Williams & Wilkins, 1996.
- Whelton PK, He J, Cutler JA, et al. Effects of oral potassium on blood pressure. Meta-analysis of randomized controlled clinical trials. JAMA 1997;277:1624-32. PubMed
- Phillips, C. O., Kashani, A., Ko, D. K., Francis, G., and Krumholz, H. M. Adverse effects of combination angiotensin II receptor blockers plus angiotensin-converting enzyme inhibitors for left ventricular dysfunction: a quantitative review of data from ra DOI
- Altieri, P. I., Herrero, C., Suero, R., and Ortiz, A. Bleeding duodenal ulcer in a patient taking slow-releasing potassium tablets. Bol.Asoc.Med P.R. 1977;69(8):276.
- Raf, L. E. Enteric-coated potassium chloride tablets and ulcer of the small intestine. Acta Chir Scand Suppl 1967;(374):1-87.
- Potassium chloride oral solution [package insert]. Allentown, PA: Lehigh Valley Technologies, Inc.; 2014.
- Potassium chloride injection [package insert]. Lake Forest, IL: Hospira Inc.; 2009.
- Patel RB, Tannenbaum S, Viana-Tejedor A, et al. Serum potassium levels, cardiac arrhythmias, and mortality following non-ST-elevation myocardial infarction or unstable angina: insights from MERLIN-TIMI 36. Eur Heart J Acute Cardiovasc Care 2017 Feb;6(1):1 PubMed
- Malta D, Arcand J, Ravindran A, Floras V, Allard JP, Newton GE. Adequate intake of potassium does not cause hyperkalemia in hypertensive individuals taking medications that antagonize the renin angiotensin aldosterone system. Am J Clin Nutr 2016 Oct;104(4 PubMed
- Keskin M, Kaya A, Tatlisu MA, et al. The effect of serum potassium level on in-hospital and long-term mortality in ST elevation myocardial infarction. Int J cardiol. 2016 Oct 15;221:505-10.
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
Calcium 62 references
- Shils M, Olson A, Shike M. Modern Nutrition in Health and Disease. 8th ed. Philadelphia, PA: Lea and Febiger, 1994.
- Hernandez-Avila M, Gonzalez-Cossio T, Hernandez-Avila JE, et al. Dietary calcium supplements to lower blood lead levels in lactating women: a randomized placebo-controlled trial. Epidemiology 2003;14:206-12.. PubMed
- Thys-Jacobs S, Ceccarelli S, Bierman A, et al. Calcium supplementation in premenstrual syndrome: a randomized crossover trial. J Gen Intern Med 1989;4:183-9. PubMed
- Maton PN, Burton ME. Antacids revisited: a review of their clinical pharmacology and recommended therapeutic use. Drugs 1999;57:855-70.
- Clemens JD, Feinstein AR. Calcium carbonate and constipation: a historical review of medical mythopoeia. Gastroenterology 1977;72:957-61. DOI
- Saunders D, Sillery J, Chapman R. Effect of calcium carbonate and aluminum hydroxide on human intestinal function. Dig Dis Sci 1988;33:409-13. PubMed
- Friedman PA, Bushinsky DA. Diuretic effects on calcium metabolism. Semin Nephrol 1999;19:551-6.
- Koo WK, Walters JC, Esterlitz J, et al. Maternal calcium supplementation and fetal bone mineralization. Obstet Gynecol 1999;94:577-82. DOI
- Raman L, Rajalakshmi K, Krishnamachari KAVR, et al. Effect of calcium supplementation to undernourished mothers during pregnancy on the bone density of the neonates. Am J Clin Nutr 1978; 31:466-9. DOI
- Murry JJ, Healy MD. Drug-mineral interactions: a new responsibility for the hospital dietician. J Am Diet Assoc 1991;91:66-73.
- Chan JM, Giovannucci E, Andersson SO, et al. Dairy products, calcium, phosphorous, vitamin D, and risk of prostate cancer. Cancer Causes Control 1998;9:559-66.
- Butner LE, Fulco PP, Feldman G, et al. Calcium carbonate-induced hypothyroidism. Ann Intern Med 2000:132:595. PubMed
- Schneyer CR. Calcium carbonate and reduction of levothyroxine efficacy. JAMA 1998;279:750. PubMed
- Moser LR, Smythe MA, Tisdale JE. The use of calcium salts in the prevention and management of verapamil-induced hypotension. Ann Pharmacother 2000;34:622-9. PubMed
- Singh N, Singh PN, Hershman JM. Effect of calcium carbonate on the absorption of levothyroxine. JAMA 2000;283:2822-5. PubMed
- Kahela P, Anttila M, Tikkanen R, Sundquist H. Effect of food, food constituents and fluid volume on the bioavailability of sotalol. Acta Pharmacol Toxicol (Copenh) 1979;44:7-12.. PubMed
- Pletz MW, Petzold P, Allen A, et al. Effect of calcium carbonate on bioavailability of orally administered gemifloxacin. Antimicrob Agents Chemother 2003;47:2158-60.. PubMed
- Bar-Or D, Yoel G. Calcium and calciferol antagonize effect of verapamil in atrial fibrillation. Br Med J 1981;282:1585-6.
- Decktor DL, Robinson M, Maton PN, et al. Effects of aluminum/magnesium hydroxide and calcium carbonate on esophageal and gastric pH in subjects with heartburn. Am J Ther 1995;2:546-52. PubMed
- Simoneau G. Absence of rebound effect with calcium carbonate. Eur J Drug Metab Pharmacokinet 1996;21:351-7. PubMed
- Peters ML, Leonard M, Licata AA. Role of alendronate and risedronate in preventing and treating osteoporosis. Cleve Clin J Med 2001;68:945-51. PubMed
- Bourke JF, Mumford R, Whittaker P, et al. The effects of topical calcipotriol on systemic calcium homeostasis in patients with chronic plaque psoriasis. J Am Acad Dermatol 1997;37:929-34.
- Gueguen L, Pointillart A. The bioavailability of dietary calcium. J Am Coll Nutr 2000;19:119s-136s. PubMed
- Vella A, Gerber TC, Hayes DL, Reeder GS. Digoxin, hypercalcaemia, and cardiac conduction. Postgrad Med J 1999;75:554-6. PubMed
- Bania TC, Blaufeux B, Hughes S, et al. Calcium and digoxin vs. calcium alone for severe verapamil toxicity. Acad Emerg Med 2000;7:1089-96. PubMed
- Tseng M, Breslow RA, Graubard BI, Ziegler RG. Dairy, calcium, and vitamin D intakes and prostate cancer risk in the National Health and Nutrition Examination Epidemiologic Follow-up Study cohort. Am J Clin Nutr 2005;81:1147-54. PubMed
- Weingarten MA, Zalmanovici A, Yaphe J. Dietary calcium supplementation for preventing colorectal cancer and adenomatous polyps. Cochrane Database Syst Rev 2004;(1):CD003548. PubMed
- Tavani A, Bertuccio P, Bosetti C, et al. Dietary intake of calcium, vitamin D, phosphorus and the risk of prostate cancer. Eur Urol 2005;48:27-33. PubMed
- Giovannucci E, Liu Y, Stampfer MJ, Willett WC. A prospective study of calcium intake and incident and fatal prostate cancer. Cancer Epidemiol Biomarkers Prev 2006;15:203-10. PubMed
- Rocephin (ceftriaxone) and calcium interaction. Pharmacist's Letter / Prescriber's Letter 2007;23(10):231005.
- Bolland MJ, Barber PA, Doughty RN, et al. Vascular events in healthy older women receiving calcium supplementation: randomised control trial. BMJ 2008;336:262-6.
- Bolland MJ, Avenell A, Baron JA, et al. Effect of calcium supplements on risk of myocardial infarction and cardiovascular events: meta-analysis. BMJ 2010;341:c3691. PubMed
- Calcium supplementation and vascular events. Pharmacist's Letter / Prescriber's Letter 2008;24(3):240306.
- Dietary reference intakes for calcium and vitamin D. Institute of Medicine, November 30, 2010. Available at: http://www.iom.edu/~/media/Files/Report%20Files/2010/Dietary-Reference-Intakes-for-Calcium-and-Vitamin-D/Vitamin%20D%20and%20Calcium%202010%20Repo
- Coburn JW, Mischel MG, Goodman WG, et al. Calcium citrate markedly enhances aluminum absorption from aluminum hydroxide. Am J Kidney Dis. 1991;17(6):708-11. PubMed
- Bradley JS, Wassel RT, Lee L, et al. Intravenous ceftriaxone and calcium in the neonate: assessing the risk for cardiopulmonary adverse events. Pediatrics. 2009;123(4):e609-13. PubMed
- Kays MB, Overholser BR, Mueller BA, et al. Effects of sevelamer hydrochloride and calcium acetate on the oral bioavailability of ciprofloxacin. Am J Kidney Dis. 2003;42(6):1253-9. PubMed
- Neuhofel, A. L., Wilton, J. H., Victory, J. M., Hejmanowsk, L. G., and Amsden, G. W. Lack of bioequivalence of ciprofloxacin when administered with calcium-fortified orange juice: a new twist on an old interaction. J Clin Pharmacol. 2002;42(4):461-466. DOI
- Dickinson, H. O., Nicolson, D. J., Cook, J. V., Campbell, F., Beyer, F. R., Ford, G. A., and Mason, J. Calcium supplementation for the management of primary hypertension in adults. Cochrane.Database.Syst.Rev. 2006;(2):CD004639. PubMed
- Jones, B. J. and Twomey, P. J. Requesting patterns for serum calcium concentration in patients on long-term lithium therapy. Int J Clin Pract. 2009;63(1):170-172. PubMed
- Levine, M., Nikkanen, H., and Pallin, D. J. The effects of intravenous calcium in patients with digoxin toxicity. J Emerg.Med. 2011;40(1):41-46. PubMed
- Castelo-Branco, C., Ciria-Recasens, M., Cancelo-Hidalgo, M. J., Palacios, S., Haya-Palazuelos, J., Carbonell-Abello, J., Blanch-Rubio, J., Martinez-Zapata, M. J., Manasanch, J., and Perez-Edo, L. Efficacy of ossein-hydroxyapatite complex compared with ca
- Li K, Kaaks R, Linseisen J, Rohrmann S. Associations of dietary calcium intake and calcium supplementation with myocardial infarction and stroke risk and overall cardiovascular mortality in the Heidelberg cohort of the European Prospective Investigation i
- Chung M, Tang AM, Fu Z. Calcium Intake and Cardiovascular Disease Risk: An Updated Systematic Review and Meta-analysis. Ann Intern Med. 2016 Oct 25. PubMed
- Nolan CR, Califano JR, Butzin CA. Influence of calcium acetate or calcium citrate on intestinal aluminum absorption. Kidney Int. 1990;38(5):937-41. PubMed
- Lewis JR, Radavelli-Bagatini S, Rejnmark L, et al. The effects of calcium supplementation on verified coronary heart disease hospitalization and death in postmenopausal women: a collaborative meta-analysis of randomized controlled trials. J Bone Miner Res PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Lappe J, Watson P, Travers-Gustafson D, Recker R, Garland C, Gorham E, Baggerly K, McDonnell SL. Effect of Vitamin D and Calcium Supplementation on Cancer Incidence in Older Women: A Randomized Clinical Trial. JAMA. 2017 Mar 28;317(12):1234-1243. PubMed
- Grove ML, Cook D. Calcium and heart attacks. Doesn't apply to most calcium prescriptions. BMJ. 2010;341:c5003. PubMed
- Insentress [package insert]. Whitehouse Station, NJ: Merck Sharp & Dohme Corp.; 2014.
- Roberts JL, Kiser JJ, Hindman JT, Meditz AL. Virologic failure with a raltegravir-containing antiretroviral regimen and concomitant calcium administration. Pharmacotherapy 2011;31(10):298e-302e. DOI
- Vitekta [package insert]. Foster City, CA: Gilead Sciences, Inc.; 2014.
- Storan ER, O'Gorman SM, Murphy A, Laing M. Case Report of Calciphylaxis Secondary to Calcium and Vitamin D<sub>3</sub> Supplementation. J Cutan Med Surg. 2017;21(2):162-163. DOI
- Jenkins DJA, Spence JD, Giovannucci EL, et al. Supplemental vitamins and minerals for CVD prevention and treatment. J Am Coll Cardiol 2018;71(22):2570-84. PubMed
- Borkenhagen JF, Connor EL, Stafstrom CE. Neonatal hypocalcemic seizures due to excessive maternal calcium ingestion. Pediatr Neurol 2013;48(6):469-71. PubMed
- WHO recommendations on antenatal care for a positive pregnancy experience. Geneva: World Health Organization; 2016 (http://www.who.int/reproductivehealth/publications/maternal_perinatal_health/ anc-positive-pregnancy-experience/en/).
- Aune D, Navarro Rosenblatt DA, Chan DS, et al. Dairy products, calcium, and prostate cancer risk: a systematic review and meta-analysis of cohort studies. Am J Clin Nutr. 2015;101(1):87-117. PubMed
- Lan T, Park Y, Colditz GA, et al. Adolescent dairy product and calcium intake in relation to later prostate cancer risk and mortality in the NIH-AARP Diet and Health Study. Cancer Causes Control. 2020;31(10):891-904. PubMed
- Zhang Y, Li Y, Liu J, et al. Association of Vitamin D or Calcium Supplementation with Cardiovascular Outcomes and Mortality: A Meta-Analysis with Trial Sequential Analysis. J Nutr Health Aging 2021;25(2):263-270. PubMed
- Myung SK, Kim HB, Lee YJ, Choi YJ, Oh SW. Calcium Supplements and Risk of Cardiovascular Disease: A Meta-Analysis of Clinical Trials. Nutrients 2021;13(2):368. PubMed
- Hetaimish B. Neonatal Calcinosis Cutis After Treatment of Hypocalcemia with Calcium Gluconate: A Report of 2 Cases. Am J Case Rep 2024;25:e943397. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Magnesium 82 references
- Rodin SM, Johnson BF. Pharmacokinetic interactions with digoxin. Clin Pharmacokinet 1988;15:227-44.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Dahle LO, Berg G, Hammar M, et al. The effect of oral magnesium substitution on pregnancy-induced leg cramps. Am J Obstet Gynecol 1995;173:175-80. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Peikert A, Wilimzig C, Kohne-Volland R. Prophylaxis of migraine with oral magnesium: results from a prospective, multi-center, placebo-controlled and double-blind randomized study. Cephalalgia 1996;16:257-63. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Washington, DC: National Academy Press, 1999. Available at: http://books.nap.edu/books/0309063507/html/index.html.
- Birrer RB, Shallash AJ, Totten V. Hypermagnesemia-induced fatality following epsom salt gargles. J Emerg Med 2002;22:185-8. PubMed
- Ryan MP. Diuretics and potassium/magnesium depletion. Directions for treatment. Am J Med 1987;82:38-47.. PubMed
- Hollifield JW. Magnesium depletion, diuretics, and arrhythmias. Am J Med 1987;82:30-7.. PubMed
- Heidenreich O. Mode of action of conventional and potassium-sparing diuretics--aspects with relevance to Mg-sparing effects. Magnesium 1984;3:248-56..
- Pfaffenrath V, Wessely P, Meyer C, et al. Magnesium in the prophylaxis of migraine--a double-blind placebo-controlled study. Cephalalgia 1996;16:436-40.. PubMed
- Wang F, Van Den Eeden SK, Ackerson LM, et al. Oral magnesium oxide prophylaxis of frequent migrainous headache in children: a randomized, double-blind, placebo-controlled trial. Headache 2003;43:601-10.. PubMed
- Sompolinsky D, Samra Z. Influence of magnesium and manganese on some biological and physical properties of tetracycline. J Bacteriol 1972;110:468-76.. PubMed
- Jeyabalan A, Caritis SN. Pharmacologic inhibition of preterm labor. Clin Obstet Gynecol 2002;45:99-113. PubMed
- Mittendorf R, Dambrosia J, Pryde PG, et al. Association between the use of antenatal magnesium sulfate in preterm labor and adverse health outcomes in infants. Am J Obstet Gynecol 2002;186:1111-8.. PubMed
- Witlin AG, Sibai BM. Magnesium sulfate therapy in preeclampsia and eclampsia. Obstet Gynecol 1998;92:883-9.. DOI
- Crowther CA, Hiller JE, Doyle LW. Magnesium sulphate for preventing preterm birth in threatened preterm labour. Cochrane Database Syst Rev 2002;4:CD001060. . PubMed
- Davey MJ, Teubner D. A randomized controlled trial of magnesium sulfate, in addition to usual care, for rate control in atrial fibrillation. Ann Emerg Med 2005;45:347-53.. PubMed
- L'Hommedieu CS, Nicholas D, Armes DA, et al. Potentiation of magnesium sulfate--induced neuromuscular weakness by gentamicin, tobramycin, and amikacin. J Pediatr 1983;102:629-31..
- Dunn CJ, Goa KL. Risedronate: a review of its pharmacological properties and clinical use in resorptive bone disease. Drugs 2001;61:685-712..
- Kass L, Weekes J, Carpenter L. Effect of magnesium supplementation on blood pressure: a meta-analysis. Eur J Clin Nutr 2012;66:411-8. PubMed
- Koontz SL, Friedman SA, Schwartz ML. Symptomatic hypocalcemia after tocolytic therapy with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 2004;190(6):1773-6. PubMed
- Snyder SW, Cardwell MS. Neuromuscular blockade with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 1989;161(1):35-6. PubMed
- Waisman GD, Mayorga LM, Cámera MI, et al. Magnesium plus nifedipine: potentiation of hypotensive effect in preeclampsia? Am J Obstet Gynecol. 1988;159(2):308-9. PubMed
- Brown DD, Juhl RP. Decreased bioavailability of digoxin due to antacids and kaolin-pectin. N Engl J Med. 1976;295(19):1034-7. PubMed
- Allen MD, Greenblatt DJ, Harmatz JS, et al. Effect of magnesium--aluminum hydroxide and kaolin--pectin on absorption of digoxin from tablets and capsules. J Clin Pharmacol. 1981;21(1):26-30. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an in vitro study. Thromb Haemost. 1996;76(1):88-93. DOI
- Ravn HB, Kristensen SD, Vissinger H, et al. Magnesium inhibits human platelets. Blood Coagul Fibrinolysis. 1996;7(2):241-4. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an infusion study in healthy volunteers. Thromb Haemost. 1996;75(6):939-44. DOI
- Neuvonen PJ, Kivistö KT. The effects of magnesium hydroxide on the absorption and efficacy of two glibenclamide preparations. Br J Clin Pharmacol. 1991;32(2):215-20. PubMed
- Kivistö KT, Neuvonen PJ. Enhancement of absorption and effect of glipizide by magnesium hydroxide. Clin Pharmacol Ther. 1991;49(1):39-43. PubMed
- Neuvonen PJ, Kivistö KT. Enhancement of drug absorption by antacids. An unrecognised drug interaction. Clin Pharmacokinet. 1994;27(2):120-8. PubMed
- Shechter, M., Merz, C. N., Paul-Labrador, M., Meisel, S. R., Rude, R. K., Molloy, M. D., Dwyer, J. H., Shah, P. K., and Kaul, S. Beneficial antithrombotic effects of the association of pharmacological oral magnesium therapy with aspirin in coronary heart
- Ganzevoort, J. W., Hoogerwaard, E. M., and van der Post, J. A. [Hypocalcemic delirium due to magnesium sulphate therapy in a pregnant woman with pre-eclampsia]. Ned.Tijdschr.Geneeskd. 8-3-2002;146(31):1453-1456.
- Horner, S. M. Efficacy of intravenous magnesium in acute myocardial infarction in reducing arrhythmias and mortality. Meta-analysis of magnesium in acute myocardial infarction. Circulation 1992;86(3):774-779. PubMed
- Azria, E., Tsatsaris, V., Goffinet, F., Kayem, G., Mignon, A., and Cabrol, D. [Magnesium sulfate in obstetrics: current data]. J Gynecol.Obstet.Biol.Reprod.(Paris) 2004;33(6 Pt 1):510-517.
- Magee, L. A., Miremadi, S., Li, J., Cheng, C., Ensom, M. H., Carleton, B., Cote, A. M., and von Dadelszen, P. Therapy with both magnesium sulfate and nifedipine does not increase the risk of serious magnesium-related maternal side effects in women with p
- Henyan, N. N., Gillespie, E. L., White, C. M., Kluger, J., and Coleman, C. I. Impact of intravenous magnesium on post-cardiothoracic surgery atrial fibrillation and length of hospital stay: a meta-analysis. Ann.Thorac.Surg. 2005;80(6):2402-2406. PubMed
- Li, J., Zhang, Q., Zhang, M., and Egger, M. Intravenous magnesium for acute myocardial infarction. Cochrane.Database.Syst.Rev. 2007;(2):CD002755. PubMed
- Doyle, L. W., Crowther, C. A., Middleton, P., Marret, S., and Rouse, D. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane.Database.Syst.Rev. 2009;(1):CD004661. PubMed
- Han, S., Crowther, C. A., and Moore, V. Magnesium maintenance therapy for preventing preterm birth after threatened preterm labour. Cochrane.Database.Syst.Rev. 2010;(7):CD000940. PubMed
- Duley, L., Gulmezoglu, A. M., Henderson-Smart, D. J., and Chou, D. Magnesium sulphate and other anticonvulsants for women with pre-eclampsia. Cochrane.Database.Syst.Rev. 2010;(11):CD000025. PubMed
- Conde-Agudelo, A., Romero, R., and Kusanovic, J. P. Nifedipine in the management of preterm labor: a systematic review and metaanalysis. Am J Obstet.Gynecol. 2011;204(2):134-20. PubMed
- Wong, G. K., Boet, R., Poon, W. S., Chan, M. T., Gin, T., Ng, S. C., and Zee, B. C. Intravenous magnesium sulphate for aneurysmal subarachnoid hemorrhage: an updated systemic review and meta-analysis. Crit Care 2011;15(1):R52. PubMed
- Magee, L., Sawchuck, D., Synnes, A., and von, Dadelszen P. SOGC Clinical Practice Guideline. Magnesium sulphate for fetal neuroprotection. J Obstet.Gynaecol.Can. 2011;33(5):516-529.
- Doyle, L. W. Antenatal magnesium sulfate and neuroprotection. Curr Opin Pediatr 2012;24(2):154-159. PubMed
- McDonald, S. D., Lutsiv, O., Dzaja, N., and Duley, L. A systematic review of maternal and infant outcomes following magnesium sulfate for pre-eclampsia/eclampsia in real-world use. Int J Gynaecol.Obstet. 2012;118(2):90-96. PubMed
- Gordon, M., Naidoo, K., Akobeng, A. K., and Thomas, A. G. Osmotic and stimulant laxatives for the management of childhood constipation. Cochrane.Database.Syst.Rev. 2012;7:CD009118. PubMed
- Dodd, J. M., Crowther, C. A., and Middleton, P. Oral betamimetics for maintenance therapy after threatened preterm labour. Cochrane.Database.Syst.Rev. 2012;12:CD003927. PubMed
- Wu, X., Wang, C., Zhu, J., Zhang, C., Zhang, Y., and Gao, Y. Meta-analysis of randomized controlled trials on magnesium in addition to beta-blocker for prevention of postoperative atrial arrhythmias after coronary artery bypass grafting. BMC.Cardiovasc.D PubMed
- Thorp, J. M., Jr., Katz, V. L., Campbell, D., and Cefalo, R. C. Hypersensitivity to magnesium sulfate. Am.J.Obstet.Gynecol. 1989;161(4):889-890. PubMed
- Duley L and Gulmezoglu AM. Magnesium sulphate versus lytic cocktail for eclampsia. Cochrane Database of Systematic Reviews 2000;(3) PubMed
- Gibbins KJ, Browning KR, Lopes VV, Anderson BL, Rouse DJ. Evaluation of the clinical use of magnesium sulfate for cerebral palsy prevention. Obstet Gynecol 2013;121(2 Pt 1):235-40. PubMed
- Ji D. Oral magnesium sulfate causes perforation during bowel preparation for fiberoptic colonoscopy in patients with colorectal cancer. J Emerg Med 2012;43(4):716-7. PubMed
- Yagi T, Naito T, Mino Y, Umemura K, Kawakami J. Impact of concomitant antacid administration on gabapentin plasma exposure and oral bioavailability in healthy adult subjects. Drug Metab Pharmacokinet 2012;27(2):248-54. PubMed
- Yamasaki M, Funakoshi S, Matsuda S, Imazu T, Takeda Y, Murakami T, Maeda Y. Interaction of magnesium oxide with gastric acid secretion inhibitors in clinical pharmacotherapy. Eur J Clin Pharmacol 2014;70(8):921-4. PubMed
- Choi ES, Jeong WJ, Ahn SH, Oh AY, Jeon YT, Do SH. Magnesium sulfate accelerates the onset of low-dose rocuronium in patients undergoing laryngeal microsurgery. J Clin Anesth. 2017 Feb;36:102-106. PubMed
- Ikee R, Toyoyama T, Endo T, Tsunoda M, Hashimoto N. Impact of sevelamer hydrochloride on serum magnesium concentrations in hemodialysis patients. Magnes Res. 2016 Apr 1;29(4):184-90. PubMed
- Miller ES, Sakowicz A, Leger E. Lange E, Yee LM. The association between receipt of intrapartum magnesium and postpartum hemorrhage. Am J Obstet Gynecol 2018;218(1 Suppl):S165.
- Rodríguez-Rubio L, Solis Garcia Del Pozo J, Nava E, Jordán J. Interaction between magnesium sulfate and neuromuscular blockers during the perioperative period. A systematic review and meta-analysis. J Clin Anesth. 2016;34:524-34. PubMed
- Brown RS. Magnesium Sulfate: Another Cause of a Solute Diuresis. Am J Kidney Dis. 2017;69(4):550-551. PubMed
- Park H, Qin R, Smith TJ, et al. North Central Cancer Treatment Group N10C2 (Alliance): a double-blind placebo-controlled study of magnesium supplements to reduce menopausal hot flashes. Menopause. 2015;22(6):627-32. PubMed
- Sakanoue M, Sanada J, Kanekura T. Skin eruption elicited by magnesium oxide (Maglax). J Dermatol. 2016;43(2):221-2.
- Iwamuro M, Saito S, Yoshioka M, et al. A Magnesium Oxide Bezoar. Intern Med. 2018;57(21):3087-3091. PubMed
- Vilchez G, Dai J, Kumar K, Mundy D, Kontopoulos E, Sokol RJ. Racial/ethnic disparities in magnesium sulfate neuroprotection: a subgroup analysis of a multicenter randomized controlled trial. J Matern Fetal Neonatal Med. 2018;31(17):2304-2311. PubMed
- Drug Safety Communication: FDA Recommends Against Prolonged Use of Magnesium Sulfate to Stop Pre-term Labor Due to Bone Changes in Exposed Babies. U.S. Food and Drug Administration (FDA), May 30, 2013. https://www.fda.gov/downloads/Drugs/DrugSafety/UCM353
- Committee Opinion: Magnesium Sulfate Use in Obstetrics. The American College of Obstetricians and Gynecologists Committee on Obstetric Practice Society for Maternal-Fetal Medicine, Number 652, January 2016. https://www.acog.org/Clinical-Guidance-and-Publi
- Kashihara Y, Terao Y, Yoda K, et al. Effects of magnesium oxide on pharmacokinetics of L-dopa/carbidopa and assessment of pharmacodynamic changes by a model-based simulation. Eur J Clin Pharmacol. 2019;75(3):351-361. PubMed
- Shepherd E, Salam RA, Manhas D, et al. Antenatal magnesium sulphate and adverse neonatal outcomes: A systematic review and meta-analysis. PLoS Med. 2019;16(12):e1002988. PubMed
- Hong JY, Hong JY, Choi YS, et al. Antenatal magnesium sulfate treatment and risk of necrotizing enterocolitis in preterm infants born at less than 32 weeks of gestation. Sci Rep. 2020;10(1):12826. PubMed
- Schuh S, Sweeney J, Rumantir M, et al. Effect of nebulized magnesium vs placebo added to albuterol on hospitalization among children with refractory acute asthma treated in the emergency department: a randomized clinical trial. JAMA. 2020;324(20):2038-20 PubMed
- Almeida CED, Carvalho LR, Andrade CVC, Nascimento PD Jr, Barros GAM, Modolo NSP. Effects of magnesium sulphate on the onset time of rocuronium at different doses: a randomized clinical trial. Braz J Anesthesiol. 2021;71(5):482-8. PubMed
- Gochi Valdovinos A, Arriaga-Redondo M, Dejuan Bitriá E, Pérez Rodríguez I, Márquez Isidro E, Blanco Bravo D. Prenatal therapy with magnesium sulphate and intestinal obstruction due to meconium in preterm newborns. An Pediatr (Engl Ed). 2022 Feb;96(2):138- PubMed
- Iio K, Kondo E, Shibata E, et al. Long-term tocolysis with magnesium sulfate as a risk factor for low bone mass: a case series. J Med Cases. 2022 Feb;13(2):47-50. PubMed
- Eiraku K, Uozumi Y, Hieda M, Maruyama T, Nomura H. A senile case of heart failure associated with hypermagnesemia induced by magnesium-containing laxative agent. Geriatr Gerontol Int. 2022;22(10):897-899.
- Enayati A, Gin JH, Sajeev JK, et al. Efficacy of intravenous magnesium for the management of non-post operative atrial fibrillation with rapid ventricular response: A systematic review and meta-analysis. J Cardiovasc Electrophysiol 2023;34(5):1286-1295. PubMed
- Su YH, Luo DC, Pang Y. Effects of intraoperative Magnesium sulfate infusion on emergency agitation during general anesthesia in patients undergoing radical mastectomy: a randomized controlled study. BMC Anesthesiol 2023;23(1):326. PubMed
- Han J, Park HY, Shin HJ, Chung SH, Do SH. Effects of magnesium sulphate on neostigmine-induced recovery from moderate neuromuscular blockade with rocuronium: a randomized controlled trial. Magnes Res 2023;36(2):31-39. PubMed
- Lee AT, Cordova JC, Jamplis RP, Pomicter GR. Posterior Reversible Encephalopathy Syndrome and Eclampsia in the Setting of Magnesium Toxicity: A Case Report. A A Pract 2023;17(11):e01726. PubMed
- Darmawan D, Rengganis I, Rumende CM, et al. Effectiveness and Safety of Nebulized Magnesium as Last Line Treatment in Adults with Acute Asthma Attack: A Systematic Review and Meta-Analysis. Acta Med Indones 2024;56(1):3-12.
- Shepherd ES, Goldsmith S, Doyle LW, et al. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane Database Syst Rev 2024;5(5):CD004661. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Lipase 1 reference
- Casper C, Hascoet JM, Ertl T, et al. Recombinant bile salt-stimulated lipase in preterm infant feeding: A randomized phase 3 study. PLoS One. 2016;11(5):e0156071. PubMed
Marshmallow 5 references
- Monographs on the medicinal uses of plant drugs. Exeter, UK: European Scientific Co-op Phytother, 1997.
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
- Hage-Sleiman R, Mroueh M, Daher CF. Pharmacological evaluation of aqueous extract of Althaea officinalis flower grown in Lebanon. Pharm Biol 2011;49(3):327-33.
Ginger 64 references
- Fischer-Rasmussen W, Kjaer SK, Dahl C, Asping U. Ginger treatment of hyperemesis gravidarum. Eur J Obstet Gynecol Reprod Biol 1991;38:19-24. PubMed
- Jewell D, Young G. Interventions for nausea and vomiting in early pregnancy. Cochrane Database Syst Rev 2000;(2):CD000145. PubMed
- Vutyavanich T, Kraisarin T, Ruangsri R. Ginger for nausea and vomiting in pregnancy: randomized, double-masked, placebo-controlled trial. Obstet Gynecol 2001;97:577-82. DOI
- Backon J. Ginger in preventing nausea and vomiting of pregnancy; a caveat due to its thromboxane synthetase activity and effect on testosterone binding. Eur J Obstet Gynecol Reprod Biol 1991;42:163-4. PubMed
- Srivastava KC. Effect of onion and ginger consumption on platelet thromboxane production in humans. Prostaglandins Leukot Essent Fatty Acids 1989;35:183-5. PubMed
- Stewart JJ, Wood MJ, Wood CD, Mims ME. Effects of ginger on motion sickness susceptibility and gastric function. Pharmacology 1991;42:111-20. PubMed
- Smith C, Crowther C, Willson K, et al. A randomized controlled trial of ginger to treat nausea and vomiting in pregnancy. Obstet Gynecol 2004;103:639-45. PubMed
- Portnoi G, Chng LA, Karimi-Tabesh L, et al. Prospective comparative study of the safety and effectiveness of ginger for the treatment of nausea and vomiting in pregnancy. Am J Obstet Gynecol 2003;189:1374-7.. PubMed
- Wigler I, Grotto I, Caspi D, Yaron M. The effects of Zintona EC (a ginger extract) on symptomatic gonarthritis. Osteoarthritis Cartilage 2003;11:783-9. PubMed
- Ghayur MN, Gilani AH. Ginger lowers blood pressure through blockade of voltage-dependent calcium channels. J Cardiovasc Pharmacol 2005;45:74-80. PubMed
- Thomson M, Al-Qattan KK, Al-Sawan SM, et al. The use of ginger (Zingiber officinale Rosc.) as a potential anti-inflammatory and antithrombotic agent. Prostaglandins Leukot Essent Fatty Acids 2002;67:475-8. PubMed
- Kanerva L, Estlander T, Jolanki R. Occupational allergic contact dermatitis from spices. Contact Dermatitis 1996;35:157-62. PubMed
- Akhani SP, Vishwakarma SL, Goyal RK. Anti-diabetic activity of Zingiber officinale in streptozotocin-induced type I diabetic rats. J Pharm Pharmacol 2004;56:101-5.
- Kruth P, Brosi E, Fux R, et al. Ginger-associated overanticoagulation by phenprocoumon. Ann Pharmacother 2004;38:257-60. PubMed
- Jiang X, Williams KM, Liauw WS, et al. Effect of ginkgo and ginger on the pharmacokinetics and pharmacodynamics of warfarin in healthy subjects. Br J Clin Pharmacol 2005;59:425-32. PubMed
- Borrelli F, Capasso R, Aviello G, et al. Effectiveness and safety of ginger in the treatment of pregnancy-induced nausea and vomiting. Obstet Gynecol 2005;105:849-56. PubMed
- Smith C, Crowther C, Wilson K et al. A randomized controlled trial of ginger to treat nausea and vomiting in pregnancy. Obstet Gynecol 2004;103:639-45. PubMed
- Jiang X, Blair EY, McLachlan AJ. Investigation of the effects of herbal medicines on warfarin response in healthy subjects: a population pharmacokinetic-pharmacodynamic modeling approach. J Clin Pharmacol 2006;46:1370-8. PubMed
- Chittumma P, Kaewkiattikun K, Wiriyasiriwach B. Comparison of the effectiveness of ginger and vitamin B6 for treatment of nausea and vomiting in early pregnancy: a randomized double-blind controlled trial. J Med Assoc Thai 2007;90:15-20.
- Ozgoli G, Goli M, Moattar F. Comparison of effects of ginger, mefenamic acid, and ibuprofen on pain in women with primary dysmenorrhea. J Altern Complement Med 2009;15:129-32. PubMed
- Black CD, Herring MP, Hurley DJ, O'Connor PJ. Ginger (Zingiber officinale) reduces muscle pain caused by eccentric exercise. J Pain 2010;11:894-903. PubMed
- Heitmann K, Nordeng H, Holst L. Safety of ginger use in pregnancy: results from a large population-based cohort study. Eur J Clin Pharmacol 2012 Jun 17. PubMed
- Ryan JL, Heckler CE, Roscoe JA, et al. Ginger (Zingiber officinale) reduces acute chemotherapy-induced nausea: a URCC CCOP study of 576 patients. Support Care Cancer. 2012;20:1479-89. PubMed
- Backon J. Ginger as an antiemetic: possible side effects due to its thromboxane synthetase activity. Anaesthesia. 1991;46(8):705-6.. PubMed
- Abebe W. Herbal medication: potential for adverse interactions with analgesic drugs. J Clin Pharm Ther. 2002;27:391-401. PubMed
- Argento A, Tiraferri E, Marzaloni M. [Oral anticoagulants and medicinal plants. An emerging interaction]. Ann Ital Med Int. 2000;15:139-43.
- Young HY, Liao JC, Chang YS, et al. Synergistic effect of ginger and nifedipine on human platelet aggregation: a study in hypertensive patients and normal volunteers. Am J Chin Med. 2006;34:545-51. PubMed
- Greenway FL, Liu Z, Martin CK, et al. Safety and efficacy of NT, an herbal supplement, in treating human obesity. Int J Obes (Lond). 2006;30:1737-41. PubMed
- Shalansky S, Lynd L, Richardson K, et al. Risk of warfarin-related bleeding events and supratherapeutic international normalized ratios associated with complementary and alternative medicine: a longitudinal analysis. Pharmacotherapy. 2007;27:1237-47. PubMed
- Lesho EP, Saullo L, Udvari-Nagy S. A 76-year-old woman with erratic anticoagulation. Cleve Clin J Med. 2004;71:651-6. PubMed
- Okonta JM, Uboh M, Obonga WO. Herb-Drug Interaction: A Case Study of Effect of Ginger on the Pharmacokinetic of Metronidazole in Rabbit. Indian Journal of Pharmaceutical Sciences (India) 2008;70(230):232. PubMed
- Chiang HM, Chao PD, Hsiu SL, et al. Ginger significantly decreased the oral bioavailability of cyclosporine in rats. Am J Chin Med. 2006;34:845-55. PubMed
- Bhandari U, Kanojia R, Pillai KK. Effect of ethanolic extract of Zingiber officinale on dyslipidaemia in diabetic rats. J Ethnopharmacol. 2005;97:227-30. PubMed
- Ojewole JA. Analgesic, antiinflammatory and hypoglycaemic effects of ethanol extract of Zingiber officinale (Roscoe) rhizomes (Zingiberaceae) in mice and rats. Phytother Res. 2006;20:764-72.
- Al-Amin ZM, Thomson M, Al-Qattan KK, et al. Anti-diabetic and hypolipidaemic properties of ginger (Zingiber officinale) in streptozotocin-induced diabetic rats. Br J Nutr. 2006;96:660-6.
- Islam MS, Choi H. Comparative effects of dietary ginger (Zingiber officinale) and garlic (Allium sativum) investigated in a type 2 diabetes model of rats. J Med Food. 2008;11:152-9.
- Cady RK, Goldstein J, Nett R, et al. A double-blind placebo-controlled pilot study of sublingual feverfew and ginger (LipiGesic M) in the treatment of migraine. Headache 2011;51:1078-86.
- Futrell, J. M. and Rietschel, R. L. Spice allergy evaluated by results of patch tests. Cutis 1993;52(5):288-290.
- Sripramote, M. and Lekhyananda, N. A randomized comparison of ginger and vitamin B6 in the treatment of nausea and vomiting of pregnancy. J Med Assoc.Thai. 2003;86(9):846-853.
- Lohsiriwat, S., Rukkiat, M., Chaikomin, R., and Leelakusolvong, S. Effect of ginger on lower esophageal sphincter pressure. J.Med.Assoc.Thai. 2010;93(3):366-372.
- Liu, P. H. and Ho, H. L. Ginger and drug bezoar induced small bowel obstruction. J R.Coll.Surg.Edinb. 1983;28(6):397-398.
- Maghbooli M, Golipour F, Moghimi Esfandabadi A, Yousefi M. Comparison between the efficacy of ginger and sumatriptan in the ablative treatment of the common migraine. Phytother Res 2014;28(3):412-5. PubMed
- Mahluji S, Attari VE, Mobasseri M, Payahoo L, Ostadrahimi A, Golzari SE. Effects of ginger (Zingiber officinale) on plasma glucose level, HbA1c and insulin sensitivity in type 2 diabetic patients. Int J Food Sci Nutr 2013;64(6):682-6.
- Mozaffari-Khosravi H, Talaei B, Jalali BA, Najarzadeh A, Mozayan MR. The effect of ginger powder supplementation on insulin resistance and glycemic indices in patients with type 2 diabetes: a randomized, double-blind, placebo-controlled trial. Complement PubMed
- Paramdeep G. Efficacy and tolerability of ginger (Zingiber officinale) in patients of osteoarthritis of knee. Indian J Physiol Pharmacol 2013;57(2):177-83.
- Rahnama P, Montazeri A, Huseini HF, Kianbakht S, Naseri M. Effect of Zingiber officinale R. rhizomes (ginger) on pain relief in primary dysmenorrhea: a placebo randomized trial. BMC Complement Altern Med 2012;12:92. PubMed
- Viljoen E, Visser J, Koen N, Musekiwa A. A systematic review and meta-analysis of the effect and safety of ginger in the treatment of pregnancy-associated nausea and vomiting. Nutr J 2014;13:20. PubMed
- Bartels EM, Folmer VN, Bliddal H, et al. Efficacy and safety of ginger in osteoarthritis patients: a meta-analysis of randomized placebo-controlled trials. Osteoarthritis Cartilage. 2015;23(1):13-21. PubMed
- Choi JS, Han JY, Ahn HK, et al. Assessment of fetal and neonatal outcomes in the offspring of women who had been treated with dried ginger (Zingiberis rhizoma siccus) for a variety of illnesses during pregnancy. J Obstet Gynaecol. 2015;35(2):125-30.
- Marx W, McKavanagh D, McCarthy AL, Bird R, Ried K, Chan A, Isenring L. The effect of ginger (Zingiber officinale) on platelet aggregation: A systematic literature review. PLoS One. 2015;10(10):e0141119. PubMed
- Crichton M, Marshall S, Marx W, McCarthy AL, Isenring E. Efficacy of ginger (Zingiber officinale) in ameliorating chemotherapy-induced nausea and vomiting and chemotherapy-related outcomes: A systematic review update and meta-analysis. J Acad Nutr Diet. 2 PubMed
- Martins LB, Rodrigues AMDS, Monteze NM, et al. Double-blind placebo-controlled randomized clinical trial of ginger (Zingiber officinale Rosc.) in the prophylactic treatment of migraine. Cephalalgia. 2020;40(1):88-95.
- Martins LB, Rodrigues AMDS, Rodrigues DF, Dos Santos LC, Teixeira AL, Ferreira AVM. Double-blind placebo-controlled randomized clinical trial of ginger (Zingiber officinale Rosc.) addition in migraine acute treatment. Cephalalgia. 2019;39(1):68-76.
- Ahad A, Raish M, Bin Jardan YA, Alam MA, Al-Mohizea AM, Al-Jenoobi FI. Effect of Hibiscus sabdariffa and Zingiber officinale on the antihypertensive activity and pharmacokinetic of losartan in hypertensive rats. Xenobiotica. 2020:1-11.
- Okuhira H, Nakatani Y, Furukawa F, Kanazawa N. Anaphylaxis to ginger induced by herbal medicine. Allergol Int. 2020;69(1):159-160. PubMed
- Yamprasert R, Chanvimalueng W, Mukkasombut N, Itharat A. Ginger extract versus Loratadine in the treatment of allergic rhinitis: a randomized controlled trial. BMC Complement Med Ther. 2020;20(1):116. PubMed
- Ebrahimzadeh A, Ebrahimzadeh A, Mirghazanfari SM, Hazrati E, Hadi S, Milajerdi A. The effect of ginger supplementation on metabolic profiles in patients with type 2 diabetes mellitus: a systematic review and meta-analysis of randomized controlled trials. PubMed
- Alam MA, Bin Jardan YA, Alzenaidy B, et al. Effect of Hibiscus sabdariffa and Zingiber officinale on pharmacokinetics and pharmacodynamics of amlodipine. J Pharm Pharmacol 2021;73(9):1151-60.
- Akbarzadeh E, Heydari M, Atarzadeh F, Jaladat AM. Chronic dysuria following ginger (Zingiber officinale) use: a case report. Galen Med J 2018;7:e1086. DOI
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Rostamkhani H, Veisi P, Niknafs B, Jafarabadi MA, Ghoreishi Z. The effect of zingiber officinale on prooxidant-antioxidant balance and glycemic control in diabetic patients with ESRD undergoing hemodialysis: a double-blind randomized control trial. BMC Co PubMed
- Husain I, Dale OR, Idrisi M, et al. Evaluation of the Herb-Drug Interaction (HDI) Potential of Zingiber officinale and Its Major Phytoconstituents. J Agric Food Chem. 2023;71(19):7521-7534.
- Committee on Practice Bulletins-Obstetrics. ACOG Practice Bulletin No. 189: Nausea And Vomiting Of Pregnancy. Obstet Gynecol. 2018;131(1):e15-e30. PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
Sodium Bicarbonate 49 references
- Ellenhorn MJ, et al. Ellenhorn's Medical Toxicology: Diagnoses and Treatment of Human Poisoning. 2nd ed. Baltimore, MD: Williams & Wilkins, 1997.
- Ritsema GH, Ellers G. Potassium supplements prevent serious hypokalemia in colon cleansing. Clin Radiol 1994;49;874-6.
- Murry JJ, Healy MD. Drug-mineral interactions: a new responsibility for the hospital dietician. J Am Diet Assoc 1991;91:66-73.
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Robertson JI. Diuretics, potassium depletion and risk of arrhythmias. Eur Heart J 1984;5(Suppl A):25-8.
- Lipworth BJ, McDevitt DG. Beta-adrenoceptor responses to inhaled salbutamol in normal subjects. Eur J Clin Pharmacol 1989;36:239-45.. PubMed
- Deenstra M, Haalboom JRE, Struyvenberg A. Decrease of plasma potassium due to inhalation of beta-2-agonists: absence of an additional effect of intravenous theophylline. Eur J Clin Invest 1988;18:162-5.. PubMed
- Braden GL, von Oeyen PT, Germain MJ, et al. Ritodrine- and terbutaline-induced hypokalemia in preterm labor: mechanisms and consequences. Kidney Int 1997;51:1867-75.. PubMed
- Shrestha M, Bidadi K, Gourlay S, Hayes J. Continuous vs intermittent albuterol, as high and low doses, in the treatment of severe acute asthma in adults. Chest 1996;110:42-7..
- Rahman ARA, McDevitt DG, Struthers AD, Lipworth BJ. The effects of enalapril and spironolactone on terbutaline-induced hypokalemia. Chest 1992;102:91-5..
- Clifton GD, Hunt BA, Patel RC, Burki NK. Effects of sequential doses of parenteral terbutaline on plasma levels of potassium and related cardiopulmonary responses. Am Rev Respir Dis 1990;141:575-9.. PubMed
- Haalboom JRE, Deenstra M, Struyvenberg A. Effect of fenoterol on plasma potassium and cardiac ectopic activity (letter). Lancet 1989;2:45. PubMed
- Raimondi GA, Rodriguez-Moncalvo JJ. Effects of beta-adrenergic agents on hypokalemia (letter). Chest 1987;91:288-9. PubMed
- Gelmont DM, Balmes JR, Yee A. Hypokalemia induced by inhaled bronchodilators. Chest 1988;94:763-6.. PubMed
- Kung M, White JR, Burki NK. The effect of subcutaneously administered terbutaline on serum potassium in asymptomatic adult asthmatics. Am Rev Respir Dis 1984;129:329-32..
- Rohr AS, Spector SL, Rachelefsky GS, et al. Efficacy of parenteral albuterol in the treatment of asthma: Comparison of its metabolic side effects with subcutaneous epinephrine. Chest 1986;89:348-51.. PubMed
- Isaac G, Holland OB. Drug-induced hypokalamia: A cause for concern. Drugs & Aging 1992;2:35-41.
- Crane J, Burgess CD, Graham AN, Maling TJB. Hypokalemic and electrocardiographic effects of aminophylline and salbutamol in obstructive airways disease. NZ Med J 1987;100:309-11. DOI
- Zantvoort FA, Derkx FHM, Boomsma F, et al. Theophylline and serum electrolytes (letter). Ann Int Med 1986;104:134-5. PubMed
- Braat MCP, Jonkers RE, Bel EH, Van Boxtel CJ. Quantification of theophylline-induced eosinopenia and hypokalamia in healthy volunteers. Clin Pharmacokinet 1992;22:231-7..
- Flack JM, Ryder KW, Strickland D, Whang R. Metabolic correlates of theophylline therapy: a concentration-related phenomenon. Ann Pharmacother 1994;28:175-9.. PubMed
- Smith SR, Kendall MJ. Metabolic responses to beta-2 stimulants. J R Coll Phys Lond 1984;18:190-4.
- Food and Drug Administration. A Catalog of FDA Approved Drug Products. Available at: http://www.accessdata.fda.gov/scripts/cder/drugsatfda/ (Accessed 28 June 2005).
- Mohammadianpanah M, Omidvari S, Mosalaei A, Ahmadloo N. Cisplatin-induced hypokalemic paralysis. Clin Ther 2004;26:1320-3. PubMed
- Panichpisal K, Angulo-Pernett F, Selhi S, Nugent KM. Gitelman-like syndrome after cisplatin therapy: a case report and literature review. BMC Nephrol 2006;7:10. PubMed
- Bjornson DC, Stephenson SR. Cisplatin-induced massive renal tubular failure with wastage of serum electrolytes. Clin Pharm 1983;2;80-3.
- Clegg, A. J., Loveman, E., Gospodarevskaya, E., Harris, P., Bird, A., Bryant, J., Scott, D. A., Davidson, P., Little, P., and Coppin, R. The safety and effectiveness of different methods of earwax removal: a systematic review and economic evaluation. Heal PubMed
- Carr, A. J., Hopkins, W. G., and Gore, C. J. Effects of acute alkalosis and acidosis on performance: a meta-analysis. Sports Med 2011;41(10):801-814. PubMed
- Proudfoot, A. T., Krenzelok, E. P., and Vale, J. A. Position Paper on urine alkalinization. J Toxicol Clin Toxicol 2004;42(1):1-26. PubMed
- Fitzgibbons, L. J. and Snoey, E. R. Severe metabolic alkalosis due to baking soda ingestion: case reports of two patients with unsuspected antacid overdose. J Emerg Med 1999;17(1):57-61. PubMed
- Barna, P. Sodium bicarbonate: burst stomachs and high sodium. J Clin Gastroenterol 1986;8(6):697-698.
- Mastrangelo, M. R. and Moore, E. W. Spontaneous rupture of the stomach in a healthy adult man after sodium bicarbonate ingestion. Ann Intern Med 1984;101(5):649-650. PubMed
- Hughes, G. S., Heald, D. L., Barker, K. B., Patel, R. K., Spillers, C. R., Watts, K. C., Batts, D. H., and Euler, A. R. The effects of gastric pH and food on the pharmacokinetics of a new oral cephalosporin, cefpodoxime proxetil. Clin Pharmacol Ther 1989; PubMed
- Neuvonen, P. J. and Karkkainen, S. Effects of charcoal, sodium bicarbonate, and ammonium chloride on chlorpropamide kinetics. Clin Pharmacol Ther 1983;33(3):386-393. PubMed
- Proudfoot AT, Krenzelok EP, Brent J, Vale JA. Does urine alkalinization increase salicylate elimination? If so, why? Toxicol Rev 2003;22(3):129-36. PubMed
- Neavyn MJ, Boyer EW, Bird SB, Babu KM. Sodium acetate as a replacement for sodium bicarbonate in medical toxicology: a review. J Med Toxicol 2013;9(3):250-4. PubMed
- Brater DC, Kaojarern S, Benet LZ, et al. Renal excretion of pseudoephedrine. Clin Pharmacol Ther 1980;28(5):690-4. PubMed
- Lemmon WT, Paschal GW Jr. Rupture of the stomach following ingestion of sodium bicarbonate. Ann Surg 1941;114(6):997-1003. PubMed
- Zer M, Chaimoff C, Dintsman M. Spontaneous rupture of the stomach following ingestion of sodium bicarbonate. Arch Surg 1970;101(4):532-3. PubMed
- Brismar B, Strandberg A, Wiklund B. Stomach rupture following ingestion of sodium bicarbonate. Acta Chir Scand Suppl 1986;530:97-9.
- Thomas SH, Stone CK. Acute toxicity from baking soda ingestion. Am J Emerg Med 1994;12(1):57-9. PubMed
- Food and Drug Administration Department of Health and Human Services. 21 CFR Part 331. Antacid Drug Products for Over-the-Counter Human Use; Amendment to Antacid Final Monograph; Proposed Rule. Federal Register. 1994;59(22):5060-5065.
- Gonzalez J, Hogg R. Metabolic alkalosis secondary to baking soda treatment of a diaper rash. Pediatrics. 1981;67:820-822. DOI
- Mahadevan U. Gastrointestinal medications in pregnancy. Best Pract Res Clin Gastroenterol. 2007;21(5):849-77. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Gurton WH, Gough LA, Sparks SA, Faghy MA, Reed KE. Sodium bicarbonate ingestion improves time-to-exhaustion cycling performance and alters estimated energy system contribution: A dose-response investigation. Front Nutr. 2020 Sep 8;7:154. PubMed
- Hilton NP, Leach NK, Craig MM, Sparks SA, McNaughton LR. Enteric-coated sodium bicarbonate attenuates gastrointestinal side-effects. Int J Sport Nutr Exerc Metab. 2019 Nov 21:1-7. PubMed
- Grgic J, Pedisic Z, Saunders B, et al. International society of sports nutrition position stand: sodium bicarbonate and exercise performance. J Int Soc Sports Nutr 2021;18(1):61. PubMed
- Hughes A, Brown A, Valento M. Hemorrhagic encephalopathy from acute baking soda ingestion. West J Emerg Med. 2016;17(5):619-22. PubMed
Papaya 14 references
- The Review of Natural Products by Facts and Comparisons. St. Louis, MO: Wolters Kluwer Co., 1999.
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- Shaw D, Leon C, Kolev S, Murray V. Traditional remedies and food supplements: a 5-year toxicological study (1991-1995). Drug Saf 1997;17:342-56.
- Mansfield LE, Ting S, Haverly RW, Yoo TJ. The incidence and clinical implications of hypersensitivity to papain in an allergic population, confirmed by blinded oral challenge. Ann Allergy 1985;55:541-3.
- Blanco C, Diaz-Perales A, Collada C, et al. Class I chitinases as potential panallergens involved in the latex-fruit syndrome. J Allergy Clin Immunol 1999;103(3 Pt 1):507-13. PubMed
- Diaz-Perales A, Collada C, Blanco C, et al. Cross-reactions in the latex-fruit syndrome: A relevant role of chitinases but not of complex asparagine-linked glycans. J Allergy Clin Immunol 1999;104:681-7. PubMed
- Castillo, R., Delgado, J., Quiralte, J., Blanco, C., and Carrillo, T. Food hypersensitivity among adult patients: epidemiological and clinical aspects. Allergol.Immunopathol.(Madr.) 1996;24(3):93-97.
- Oderinde, O., Noronha, C., Oremosu, A., Kusemiju, T., and Okanlawon, O. A. Abortifacient properties of aqueous extract of Carica papaya (Linn) seeds on female Sprague-Dawley rats. Niger.Postgrad.Med J 2002;9(2):95-98. DOI
- Danese, C., Esposito, D., D'Alfonso, V., Cirene, M., Ambrosino, M., and Colotto, M. Plasma glucose level decreases as collateral effect of fermented papaya preparation use. Clin Ter. 2006;157(3):195-198.
- Iliev, D. and Elsner, P. Generalized drug reaction due to papaya juice in throat lozenges. Dermatology 1997;194(4):364-366. PubMed
- Andersen HA, Bernatz PE, Grindlay JH. Perforation of the esophagus after use of a digestant agent: report of case and experimental study. Ann Otol Rhinol Laryngol 1959;68:890-6. PubMed
- Deiana L, Marini S, Mariotti S. Ingestion of large amounts of papaya fruit and impaired effectiveness of levothyroxine therapy. Endocr Pract 2012;18(1):98-100. PubMed
- Rodrigues M, Alves G, Francisco J, Fortuna A, Falcão A. Herb-drug pharmacokinetic interaction between Carica papaya extract and amiodarone in rats. J Pharm Pharm Sci 2014;17(3):302-15. PubMed
- Rajapakse S, de Silva NL, Weeratunga P, Rodrigo C, Sigera C, Fernando SD. Carica papaya extract in dengue: a systematic review and meta-analysis. BMC Complement Altern Med. 2019;19(1):265. PubMed
Holy Basil 8 references
- Agrawal P, Rai V, Singh RB. Randomized placebo-controlled, single blind trial of holy basil leaves in patients with noninsulin-dependent diabetes mellitus. Int J Clin Pharmacol Ther 1996;34:406-9.
- Sakina MR, Dandiya PC, Hamdard ME, Hameed A. Preliminary psychopharmacological evaluation of Ocimum sanctum leaf extract. J Ethnopharmacol 1990;28:143-50. PubMed
- Singh S, Rehan HM, Majumdar DK. Effect of Ocimum sanctum fixed oil on blood pressure, blood clotting time and pentobarbitone-induced sleeping time. J Ethnopharmacol 2001;78:139-43. PubMed
- Mondal, S., Varma, S., Bamola, V. D., Naik, S. N., Mirdha, B. R., Padhi, M. M., Mehta, N., and Mahapatra, S. C. Double-blinded randomized controlled trial for immunomodulatory effects of Tulsi (Ocimum sanctum Linn.) leaf extract on healthy volunteers. J PubMed
- Agarwal, P. and Nagesh, L. Comparative evaluation of efficacy of 0.2% Chlorhexidine, Listerine and Tulsi extract mouth rinses on salivary Streptococcus mutans count of high school children--RCT. Contemp.Clin Trials 2011;32(6):802-808. PubMed
- Vohora, S. B., Garg, S. K., and Chaudhury, R. R. Antifertility screening of plants. 3. Effect of six indigenous plants on early pregnancy in albino rats. Indian J Med Res 1969;57(5):893-899.
- Khanna S, Gupta SR, Grover JK. Effect of long term feeding of tulsi (Ocimum sanctum Linn) on reproductive performance of adult albino rats. Indian J Exp Biol 1986;24(5):302-4.
- Somasundaram G, Manimekalai K, Salwe KJ, Pandiamunian J. Evaluation of the antidiabetic effect of Ocimum sanctum in type 2 diabetes patients. Int J Life Sci Pharma Res 2012;2(3):75-81.
Rosemary 20 references
- Newall CA, Anderson LA, Philpson JD. Herbal Medicine: A Guide for Healthcare Professionals. London, UK: The Pharmaceutical Press, 1996.
- Foster S, Tyler VE. Tyler's Honest Herbal: A Sensible Guide to the Use of Herbs and Related Remedies. 3rd ed., Binghamton, NY: Haworth Herbal Press, 1993.
- The Review of Natural Products by Facts and Comparisons. St. Louis, MO: Wolters Kluwer Co., 1999.
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Cartier LC, Lehrer A, Malo JL. Occupational asthma caused by aromatic herbs. Allergy 1996;51:647-9. DOI
- Burkhard PR, Burkhardt K, Haenggeli CA, Landis T. Plant-induced seizures: reappearance of an old problem. J Neurol 1999;246:667-70. PubMed
- Swain AR, Dutton SP, Truswell AS. Salicylates in foods. J Am Diet.Assoc 1985;85(8):950-60. DOI
- Zhu BT, Loder DP, Cai MX, et al. Dietary administration of an extract from rosemary leaves enhances the liver microsomal metabolism of endogenous estrogens and decreases their uterotropic action in CD-1 mice. Carcinogenesis 1998;19(10):1821-7. PubMed
- Debersac P, Heydel JM, Amiot MJ, et al. Induction of cytochrome P450 and/or detoxication enzymes by various extracts of rosemary: description of specific patterns. Food Chem Toxicol 2001;39(9):907-18. PubMed
- Debersac P, Vernevaut MF, Amiot MJ, et al. Effects of a water-soluble extract of rosemary and its purified component rosmarinic acid on xenobiotic-metabolizing enzymes in rat liver. Food Chem Toxicol 2001;39(2):109-17. PubMed
- Lee JJ, Jin YR, Lee JH, et al. Antiplatelet activity of carnosic acid, a phenolic diterpene from Rosmarinus officinalis. Planta Med 2007;73(2):121-7.
- Yamamoto J, Yamada K, Naemura A, et al. Testing various herbs for antithrombotic effect. Nutrition 2005;21(5):580-7. PubMed
- Naemura A, Ura M, Yamashita T, et al. Long-term intake of rosemary and common thyme herbs inhibits experimental thrombosis without prolongation of bleeding time. Thromb Res 2008;122(4):517-22. PubMed
- Lee JJ, Jin YR, Lim Y, et al. Antiplatelet activity of carnosol is mediated by the inhibition of TXA2 receptor and cytosolic calcium mobilization. Vascul Pharmacol 2006;45:148-53. PubMed
- Bakirel, T., Bakirel, U., Keles, O. U., Ulgen, S. G., and Yardibi, H. In vivo assessment of antidiabetic and antioxidant activities of rosemary (Rosmarinus officinalis) in alloxan-diabetic rabbits. J Ethnopharmacol 2-28-2008;116(1):64-73. PubMed
- Erenmemisoglu, A., Saraymen, R., and Ustun, S. Effect of a Rosmarinus officinalis leave extract on plasma glucose levels in normoglycaemic and diabetic mice. Pharmazie 1997;52(8):645-646.
- Valones MAA, Silva ICG, Gueiros LAM, Leão JC, Caldas AF Jr, Carvalho AAT. Clinical assessment of rosemary-based toothpaste (Rosmarinus officinalis Linn.): A randomized controlled double-blind study. Braz Dent J. 2019;30(2):146-151. PubMed
- Quirarte-Báez SM, Zamora-Perez AL, Reyes-Estrada CA, et al. A shortened treatment with rosemary tea (rosmarinus officinalis) instead of glucose in patients with diabetes mellitus type 2 (TSD). J Popul Ther Clin Pharmacol. 2019;26(4):e18-e28.
- Al Jamal A. Effect of rosemary (Rosmarinus officinalis) on lipid profiles and blood glucose in human diabetic patients (type-2). African J. Biochem. Res. 2014;8(8):147-50. DOI
Papain 11 references
- The Review of Natural Products by Facts and Comparisons. St. Louis, MO: Wolters Kluwer Co., 1999.
- Shaw D, Leon C, Kolev S, Murray V. Traditional remedies and food supplements: a 5-year toxicological study (1991-1995). Drug Saf 1997;17:342-56.
- Shuttleworth D, Hill S, Marks R, Connelly DM. Relief of experimentally induced pruritus with a novel eutectic mixture of local anaesthetic agents. Br J Dermatol 1988;119:535-40.
- Mansfield LE, Ting S, Haverly RW, Yoo TJ. The incidence and clinical implications of hypersensitivity to papain in an allergic population, confirmed by blinded oral challenge. Ann Allergy 1985;55:541-3.
- Martin, T., Uhder, K., Kurek, R., Roeddiger, S., Schneider, L., Vogt, H. G., Heyd, R., and Zamboglou, N. Does prophylactic treatment with proteolytic enzymes reduce acute toxicity of adjuvant pelvic irradiation? Results of a double-blind randomized trial PubMed
- Walker-Renard, P. Update on the medicinal management of phytobezoars. Am J Gastroenterol. 1993;88(10):1663-1666.
- Tymoszuk D, Wiszniewska M, Walusiak-Skorupa J. Papain-induced occupational rhinoconjunctivitis and asthma - A case report. Med Pr 2016;67(1):109-12. PubMed
- Soto-Mera MT, López-Rico MR, Filgueira JF, et al. Occupational allergy to papain. Allergy 2000;55(10):983-4. PubMed
- Tarlo SM, Shaikh W, Bell B, et al. Papain-induced allergic reactions. Clin Allergy 1978;8(3):207-15. PubMed
- Baur X, König G, Bencze K, Fruhmann G. Clinical symptoms and results of skin test, RAST and bronchial provocation test in thirty-three papain workers: Evidence for strong immunogenic potency and clinically relevant proteolytic e?ects of airborne papain. C
- Novey HS, Keenan WJ, Fairshter RD, Wells ID, Wilson AF, Culver BD. Pulmonary disease in workers exposed to papain: clinico-physiological and immunological studies. Clin Allergy 1980;10(6):721-31. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC