
Sleep Advance Ingredients & Drug Interactions
What is this page for?
First and foremost: checking Sleep Advance against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Sleep Advance is a dietary supplement by Logos Nutritionals with 7 active ingredients. Its ingredients are commonly taken for trouble falling asleep (insomnia), jet lag, delayed sleep phase syndrome.Based on those ingredients, 1,624 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Melatonin, Phellodendron, Powder, L-Theanine. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Sleep Advance by Logos Nutritionals
Ask about any prescription or over-the-counter medication and we check it for interactions with Sleep Advance by Logos Nutritionals — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Sleep Advance by Logos Nutritionals
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
Sleep Advance contains seven active ingredients. Melatonin is the primary sleep-promoting ingredient.
L-theanine and 5-hydroxytryptophan (5-HTP) are amino acid derivatives that support relaxation and mood. Magnesium is a mineral cofactor involved in over 300 body processes, including muscle and nervous system function.
Mucuna pruriens seed extract is a plant source of levodopa (an active compound). Phellodendron powder is a traditional herb that contains berberine.
Gamma-aminobutyric acid (GABA) is a neurotransmitter that supports relaxation. The product also contains several inactive ingredients—rice powder, cellulose, magnesium stearate, silicon dioxide, calcium carbonate, and calcium phosphate—as binders and fillers.
Does it work?
Strong evidence
Evidence for Sleep Advance's ingredients is mixed. Melatonin is likely effective for non-24-hour sleep-wake disorder and delayed sleep phase syndrome (DSPS), and possibly effective for reducing pre-procedural anxiety and sunburn.
L-theanine is possibly effective for cognitive function, but evidence for other uses like anxiety or Alzheimer's disease is insufficient. 5-HTP is possibly effective for depression but possibly ineffective for Down syndrome; evidence for panic disorder and other conditions is insufficient.
Magnesium is effective for dyspepsia, constipation, hypomagnesemia, and pre-eclampsia. For the remaining ingredients—Mucuna pruriens, phellodendron, and GABA—the evidence for any of their proposed uses is either insufficient or not established in our data.
The product is marketed as a sleep aid, but only melatonin, L-theanine, and 5-HTP have even limited evidence for sleep-related effects.
How safe is it?
Well-documented data
Melatonin is generally well tolerated for short-term use, though long-term safety is less certain. Common side effects include dizziness, drowsiness, headache, and nausea.
Rarely, melatonin may increase seizure risk or cause mood changes, hallucinations, or reduced fertility in men. Safety data advises against use during pregnancy and breastfeeding.
L-theanine is generally well tolerated short-term in healthy adults but may cause headaches, drowsiness, and increased dream activity; long-term safety is not well studied. There is not enough data to use it during pregnancy or while breastfeeding.
5-HTP is generally well tolerated short-term but commonly causes abdominal pain, nausea, diarrhea, drowsiness, and fatigue—effects that may depend on dose and diminish over time. Rare serious effects include hallucinations and mania.
Safety data advises against use in pregnancy and while breastfeeding. Magnesium is generally safe at recommended doses; common side effects are diarrhea, nausea, and vomiting.
Magnesium is needed in pregnancy but should be used only under medical guidance; normal dietary amounts are appropriate while breastfeeding. Mucuna pruriens contains the active compound levodopa and should be used carefully under professional guidance; safety data advises against it during pregnancy and breastfeeding because levodopa can lower prolactin and reduce milk supply.
Phellodendron has limited human safety data and should be avoided in pregnancy and while breastfeeding due to berberine. GABA is often well tolerated short-term but can cause drowsiness, gastric upset, and muscle weakness; long-term safety is not well studied, and there is insufficient data for pregnancy or breastfeeding.
Meds to double-check
Major interaction found
Before taking Sleep Advance, double-check your medications if you take any of the following: levodopa/carbidopa (Sinemet) or other Parkinson's drugs—magnesium can substantially reduce their absorption; blood pressure medications, especially nifedipine—multiple ingredients may lower or interfere with them; blood thinners like warfarin or antiplatelet drugs—melatonin and phellodendron may increase bleeding risk; seizure medications (anticonvulsants)—melatonin may reduce their effectiveness and increase seizure risk; diabetes drugs—melatonin and phellodendron may lower blood sugar; antidepressants, especially SSRIs or MAOIs—5-HTP can cause dangerous serotonergic effects or hypertensive crisis; or any CNS depressants (sedatives, sleep aids, opioids, alcohol). No interactions are documented for the inactive ingredients we could check.
The bottom line
Scorecard at a glanceFully disclosed formula with clinical evidence supporting its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
Sleep Advance combines ingredients with some evidence for sleep support (melatonin, L-theanine, 5-HTP) alongside others with limited or unproven effectiveness. If you take blood pressure medication, blood thinners, seizure medication, diabetes drugs, antidepressants, or any Parkinson's medication, talk to your pharmacist or doctor before using this product—the interaction risks are real and potentially serious.
Even if you don't take any of those, this product is best used short-term and under professional guidance, especially if you have a history of seizures, mood disorders, or low blood pressure.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 7 of 7 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jul 24, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Sleep Advance, straight from the product label.
| Brand | Logos Nutritionals |
|---|---|
| Barcode (UPC) | 850045673277 |
| Net contents | 60 Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Jul 24, 2025 |
| DSLD ID | 335733 |
| Product type | Other Combinations |
| Supplement form | Capsule |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Women (not pregnant or lactating) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for Sleep Advance by Logos Nutritionals, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Melatonin | 2 mg | -- |
| L-Theanine | 400 mg | -- |
| 5-Hydroxytryptophan | 50 mg | -- |
| Magnesium | 200 mg | 48% |
| Mucuna pruriens Seed Extract | 100 mg | -- |
| Phellodendron, Powder | 100 mg | -- |
| Gamma-Aminobutyric Acid | 100 mg | -- |
Other ingredients: Rice, Powder, Cellulose, Magnesium Stearate, Silicon Dioxide, Calcium Carbonate, Calcium Phosphate
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Suggested/Recommended/Usage/Directions
Suggested use: 1 to 2 capsules taken at bedtime or as directed by a healthcare professional.
Precautions
Caution: For relief of occasional sleeplessness only. Do not exceed the recommended dose. Avoid driving or performing other potentially dangerous tasks while taking this formula. If you have questions about the advisability of taking this product, consult a physician prior to use.
This product is not intended for pregnant or nursing mothers, children under the age of 18, or individuals taking any prescription medication including anti-depressants.
This product is not intended for pregnant or nursing mothers, children under the age of 18, or individuals taking any prescription medication including anti-depressants. Keep out of the reach of children.
This product is manufactured and packaged in a facility which may also process milk, soy, wheat, egg, peanuts, tree nuts, fish and crustacean shellfish.
Do not use if safety seal is damaged or missing.
Storage
Store in a cool, dry place.
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure, or prevent any disease.
Formulation
We back our products with an unconditional satisfaction guarantee!
Night time formula
General Statements
Questions and comments - Call 800-556-5530 Or visit our website: www.logosnutritionals.com
Brand IP Statement(s)
Copyright 2022 Logos
Seals/Symbols
Sourced from a GMP Certified Facility Good Manufacturing Practice Quality Assured Lab Verified 3rd Party Tested Night time formula Purity Potency Renew your health, naturally
FDA Statement of Identity
Dietary Supplement
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
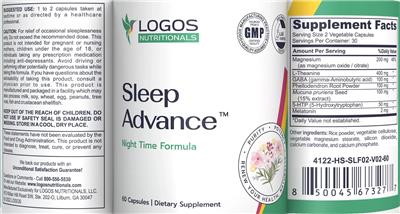
Sleep Advance by Logos Nutritionals label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Sleep Advance by Logos Nutritionals
These are the 7 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Vegetable Capsule(s) Dosage formCapsule Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Melatonin
Interacts with1,461 drugs
Melatonin is a hormone your body makes naturally to help control your sleep-wake cycle, and the supplement form is widely used to help with sleep timi...
Melatonin monograph & interactionsL-Theanine
Interacts with565 drugs
Theanine (usually L-theanine) is an amino acid found naturally in tea leaves that many people take to feel calmer and less stressed without strong dro...
L-Theanine monograph & interactions5-Hydroxytryptophan
Interacts with398 drugs
5-HTP is a compound your body uses to make serotonin, and people take it as a supplement hoping to improve mood, sleep, and headaches. Some early rese...
5-Hydroxytryptophan monograph & interactionsMagnesium
Interacts with295 drugs
Magnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preven...
Magnesium monograph & interactionsMucuna pruriens Seed Extract
Interacts with193 drugs
Cowhage (Mucuna pruriens) is a tropical legume best known as a natural source of L-dopa, the compound the body turns into dopamine. It is most studied...
Mucuna pruriens Seed Extract monograph & interactionsPhellodendron, Powder
Interacts with1,160 drugs
Phellodendron is a traditional Chinese medicine bark (Huang Bai) that contains berberine and other plant compounds with antimicrobial and anti-inflamm...
Phellodendron, Powder monograph & interactionsGamma-Aminobutyric Acid
Interacts with419 drugs
GABA is a calming chemical messenger (neurotransmitter) that your body makes on its own, and it is sold as a supplement for stress, anxiety, and sleep...
Gamma-Aminobutyric Acid monograph & interactionsOther (inactive) ingredients: Rice, Powder, Cellulose, Magnesium Stearate, Silicon Dioxide, Calcium Carbonate, Calcium Phosphate. These complete the product’s ingredient list but are not active constituents.
Sleep Advance by Logos Nutritionals Drug Interactions
HelloPharmacist Interaction Report
Sleep Advance by Logos Nutritionals contains seven active ingredients, several of which interact with medications.
The most serious concern is magnesium, which can substantially reduce the absorption of levodopa/carbidopa (Sinemet) — a medication for Parkinson's disease — by up to 35% for levodopa and 81% for carbidopa. This is a major-severity interaction that could significantly weaken your treatment.
Read the full breakdown — every affected drug type, severity by severity
Melatonin, the product's primary sleep ingredient, carries multiple moderate-severity interactions. It may reduce the effectiveness of extended-release nifedipine (a blood pressure medication), increase bleeding risk with blood thinners like warfarin, interfere with seizure medications, affect blood sugar control with diabetes drugs, and either raise or lower blood pressure when used with blood pressure medications.
Additionally, 5-hydroxytryptophan can increase serotonin effects dangerously with certain antidepressants and other serotonergic drugs, and has additive sedating effects with other CNS depressants. Phellodendron (which contains berberine) may inhibit liver enzymes that metabolize many drugs, potentially raising levels of those medications, and may increase bleeding risk and lower blood sugar.
Mucuna pruriens seed extract is another major concern — it contains levodopa and can cause dangerously high blood pressure with certain blood pressure medications or MAOIs, and increases the risk of levodopa-related side effects if you're already taking that drug. L-theanine and GABA carry only minor interactions with CNS depressants and some antihypertensive drugs.
Altogether, these interactions span 1,606 individual medications.
Before starting Sleep Advance, check your exact medications with the tool on this page—especially if you take any blood pressure medication, blood thinner, seizure medication, diabetes drug, antidepressant, Parkinson's medication, or MAOI.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Sleep Advance?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Sleep Advance interact with 1,624 drugs. Click any drug to see the details.
7 of the 7 ingredients in Sleep Advance interact with drugs. Each result below shows which ingredient is responsible. Melatonin Phellodendron, Powder L-Theanine Gamma-Aminobutyric Acid 5-Hydroxytryptophan Magnesium Mucuna pruriens Seed Extract
AmphetamineAdensys XR-ODT, Adzenys ER, Dyanavel XR, Mydayis
How Amphetamine interacts with Sleep Advance — through 3 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Amphetamine interactionMelatoninSeizure Threshold Lowering Drugs, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, taking melatonin with drugs that lower the seizure threshold might increase the risk of seizure activity.
Read the full Melatonin + Amphetamine interactionPhellodendron, PowderCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, phellodendron might increase serum levels of drugs metabolized by CYP2D6.
Read the full Phellodendron, Powder + Amphetamine interactionBenserazide, LevodopaMadopar, Prolopa
How Benserazide, Levodopa interacts with Sleep Advance — through 3 ingredients. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Benserazide, Levodopa interactionMucuna Pruriens Seed ExtractLevodopa Major
Interaction Summary
Concomitant use can increase the risk of levodopa-related adverse effects.
Read the full Mucuna Pruriens Seed Extract + Benserazide, Levodopa interactionMelatoninSeizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, taking melatonin with drugs that lower the seizure threshold might increase the risk of seizure activity.
Read the full Melatonin + Benserazide, Levodopa interactionCarbidopaLodosyn
How Carbidopa interacts with Sleep Advance — through 2 ingredients. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa interaction5-hydroxytryptophanCarbidopa (lodosyn) Moderate
Interaction Summary
Combining 5-HTP and carbidopa can increase the risk of serotonergic side effects.
Read the full 5-hydroxytryptophan + Carbidopa interactionCarbidopa, LevodopaDhivy, Rytary, Sinemet, Sinemet CR
How Carbidopa, Levodopa interacts with Sleep Advance — through 4 ingredients. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa, Levodopa interactionMucuna Pruriens Seed ExtractLevodopa Major
Interaction Summary
Concomitant use can increase the risk of levodopa-related adverse effects.
Read the full Mucuna Pruriens Seed Extract + Carbidopa, Levodopa interaction5-hydroxytryptophanCarbidopa (lodosyn) Moderate
Interaction Summary
Combining 5-HTP and carbidopa can increase the risk of serotonergic side effects.
Read the full 5-hydroxytryptophan + Carbidopa, Levodopa interactionMelatoninSeizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, taking melatonin with drugs that lower the seizure threshold might increase the risk of seizure activity.
Read the full Melatonin + Carbidopa, Levodopa interactionCarbidopa, Levodopa, EntacaponeStalevo
How Carbidopa, Levodopa, Entacapone interacts with Sleep Advance — through 4 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractLevodopa Major
Interaction Summary
Concomitant use can increase the risk of levodopa-related adverse effects.
Read the full Mucuna Pruriens Seed Extract + Carbidopa, Levodopa, Entacapone interactionMagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa, Levodopa, Entacapone interaction5-hydroxytryptophanCarbidopa (lodosyn) Moderate
Interaction Summary
Combining 5-HTP and carbidopa can increase the risk of serotonergic side effects.
Read the full 5-hydroxytryptophan + Carbidopa, Levodopa, Entacapone interactionMelatoninSeizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, taking melatonin with drugs that lower the seizure threshold might increase the risk of seizure activity.
Read the full Melatonin + Carbidopa, Levodopa, Entacapone interactionChlorothiazide, MethyldopaAldochlor, Aldoclor 150, Aldoclor 250
How Chlorothiazide, Methyldopa interacts with Sleep Advance — through 5 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMethyldopa (aldomet) Major
Interaction Summary
Theoretically, concomitant use of cowhage and methyldopa might increase the risk of hypotension.
Read the full Mucuna Pruriens Seed Extract + Chlorothiazide, Methyldopa interactionPhellodendron, PowderAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, phellodendron might have additive effects with antihypertensive drugs.
Read the full Phellodendron, Powder + Chlorothiazide, Methyldopa interactionL-theanineAntihypertensive Drugs Moderate
Interaction Summary
Theanine might lower blood pressure, potentiating the effects of antihypertensive drugs.
Read the full L-theanine + Chlorothiazide, Methyldopa interactionGamma-aminobutyric AcidAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking GABA with antihypertensive drugs might increase the risk of hypotension.
Read the full Gamma-aminobutyric Acid + Chlorothiazide, Methyldopa interactionMelatoninAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking melatonin with antihypertensive drugs might increase the risk of hypotension or hypertension.
Read the full Melatonin + Chlorothiazide, Methyldopa interactionHydrochlorothiazide, MethyldopaAldoril 15, Aldoril 25, Aldoril D30, Methazide
How Hydrochlorothiazide, Methyldopa interacts with Sleep Advance — through 5 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMethyldopa (aldomet) Major
Interaction Summary
Theoretically, concomitant use of cowhage and methyldopa might increase the risk of hypotension.
Read the full Mucuna Pruriens Seed Extract + Hydrochlorothiazide, Methyldopa interactionL-theanineAntihypertensive Drugs Moderate
Interaction Summary
Theanine might lower blood pressure, potentiating the effects of antihypertensive drugs.
Read the full L-theanine + Hydrochlorothiazide, Methyldopa interactionPhellodendron, PowderAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, phellodendron might have additive effects with antihypertensive drugs.
Read the full Phellodendron, Powder + Hydrochlorothiazide, Methyldopa interactionGamma-aminobutyric AcidAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking GABA with antihypertensive drugs might increase the risk of hypotension.
Read the full Gamma-aminobutyric Acid + Hydrochlorothiazide, Methyldopa interactionMelatoninAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking melatonin with antihypertensive drugs might increase the risk of hypotension or hypertension.
Read the full Melatonin + Hydrochlorothiazide, Methyldopa interactionIsocarboxazidMarplan
How Isocarboxazid interacts with Sleep Advance — through 3 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Isocarboxazid interaction5-hydroxytryptophanSerotonergic Drugs Moderate
Interaction Summary
Combining serotonergic drugs with 5-HTP might cause additive serotonergic effects.
Read the full 5-hydroxytryptophan + Isocarboxazid interactionL-theanineSerotonergic Drugs Minor
Interaction Summary
Clinical studies regarding the effects of L-theanine on serotonin levels are conflicting.
Read the full L-theanine + Isocarboxazid interactionLevodopaInbrija, Larodopa
How Levodopa interacts with Sleep Advance — through 3 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractLevodopa Major
Interaction Summary
Concomitant use can increase the risk of levodopa-related adverse effects.
Read the full Mucuna Pruriens Seed Extract + Levodopa interactionMagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Levodopa interactionMelatoninSeizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, taking melatonin with drugs that lower the seizure threshold might increase the risk of seizure activity.
Read the full Melatonin + Levodopa interactionLevodopa, CarbidopaDuodopa
How Levodopa, Carbidopa interacts with Sleep Advance — through 4 ingredients. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Levodopa, Carbidopa interactionMucuna Pruriens Seed ExtractLevodopa Major
Interaction Summary
Concomitant use can increase the risk of levodopa-related adverse effects.
Read the full Mucuna Pruriens Seed Extract + Levodopa, Carbidopa interactionMelatoninSeizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, taking melatonin with drugs that lower the seizure threshold might increase the risk of seizure activity.
Read the full Melatonin + Levodopa, Carbidopa interaction5-hydroxytryptophanCarbidopa (lodosyn) Moderate
Interaction Summary
Combining 5-HTP and carbidopa can increase the risk of serotonergic side effects.
Read the full 5-hydroxytryptophan + Levodopa, Carbidopa interactionMethyldopaAldomet, Methyldopa
How Methyldopa interacts with Sleep Advance — through 5 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMethyldopa (aldomet) Major
Interaction Summary
Theoretically, concomitant use of cowhage and methyldopa might increase the risk of hypotension.
Read the full Mucuna Pruriens Seed Extract + Methyldopa interactionPhellodendron, PowderAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, phellodendron might have additive effects with antihypertensive drugs.
Read the full Phellodendron, Powder + Methyldopa interactionL-theanineAntihypertensive Drugs Moderate
Interaction Summary
Theanine might lower blood pressure, potentiating the effects of antihypertensive drugs.
Read the full L-theanine + Methyldopa interactionMelatoninAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking melatonin with antihypertensive drugs might increase the risk of hypotension or hypertension.
Read the full Melatonin + Methyldopa interactionGamma-aminobutyric AcidAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking GABA with antihypertensive drugs might increase the risk of hypotension.
Read the full Gamma-aminobutyric Acid + Methyldopa interactionMoclobemideManerix, Moclobemide
How Moclobemide interacts with Sleep Advance — through 2 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Moclobemide interactionMelatoninCytochrome P450 2c19 (cyp2c19) Substrates Moderate
Interaction Summary
Theoretically, melatonin might increase levels of drugs metabolized by CYP2C19.
Read the full Melatonin + Moclobemide interactionOzanimod HydrochlorideZeposia
How Ozanimod Hydrochloride interacts with Sleep Advance — through 2 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Ozanimod Hydrochloride interactionMelatoninImmunosuppressants Moderate
Interaction Summary
Theoretically, melatonin might interfere with immunosuppressive therapy.
Read the full Melatonin + Ozanimod Hydrochloride interactionPhenelzine SulfateNardil
How Phenelzine Sulfate interacts with Sleep Advance — through 6 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Phenelzine Sulfate interactionPhellodendron, PowderCns Depressants Moderate
Interaction Summary
Theoretically, phellodendron might increase the sedative effects of CNS depressants.
Read the full Phellodendron, Powder + Phenelzine Sulfate interactionMelatoninCns Depressants Moderate
Interaction Summary
Theoretically, taking melatonin might increase the sedative effects of CNS depressants.
Read the full Melatonin + Phenelzine Sulfate interaction5-hydroxytryptophanCns Depressants, Serotonergic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of 5-HTP with medications that cause sedation might have additive effects.
Read the full 5-hydroxytryptophan + Phenelzine Sulfate interactionL-theanineSerotonergic Drugs, Cns Depressants Minor
Interaction Summary
Clinical studies regarding the effects of L-theanine on serotonin levels are conflicting.
Read the full L-theanine + Phenelzine Sulfate interactionGamma-aminobutyric AcidCns Depressants Minor
Interaction Summary
Theoretically, GABA might have additive sedative effects when used in conjunction with CNS depressants.
Read the full Gamma-aminobutyric Acid + Phenelzine Sulfate interactionRasagilineAzilect
How Rasagiline interacts with Sleep Advance — through 4 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Rasagiline interactionMelatoninCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, melatonin might increase levels of drugs metabolized by CYP1A2.
Read the full Melatonin + Rasagiline interaction5-hydroxytryptophanSerotonergic Drugs Moderate
Interaction Summary
Combining serotonergic drugs with 5-HTP might cause additive serotonergic effects.
Read the full 5-hydroxytryptophan + Rasagiline interactionL-theanineSerotonergic Drugs Minor
Interaction Summary
Clinical studies regarding the effects of L-theanine on serotonin levels are conflicting.
Read the full L-theanine + Rasagiline interactionSafinamide MesylateXadago
How Safinamide Mesylate interacts with Sleep Advance — through 3 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Safinamide Mesylate interaction5-hydroxytryptophanSerotonergic Drugs Moderate
Interaction Summary
Combining serotonergic drugs with 5-HTP might cause additive serotonergic effects.
Read the full 5-hydroxytryptophan + Safinamide Mesylate interactionL-theanineSerotonergic Drugs Minor
Interaction Summary
Clinical studies regarding the effects of L-theanine on serotonin levels are conflicting.
Read the full L-theanine + Safinamide Mesylate interactionSelegilineCarbex, Eldepryl, Emsam, Zelapar
How Selegiline interacts with Sleep Advance — through 3 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Selegiline interaction5-hydroxytryptophanSerotonergic Drugs Moderate
Interaction Summary
Combining serotonergic drugs with 5-HTP might cause additive serotonergic effects.
Read the full 5-hydroxytryptophan + Selegiline interactionL-theanineSerotonergic Drugs Minor
Interaction Summary
Clinical studies regarding the effects of L-theanine on serotonin levels are conflicting.
Read the full L-theanine + Selegiline interactionTranylcypromineParnate
How Tranylcypromine interacts with Sleep Advance — through 3 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens Seed Extract + Tranylcypromine interaction5-hydroxytryptophanSerotonergic Drugs Moderate
Interaction Summary
Combining serotonergic drugs with 5-HTP might cause additive serotonergic effects.
Read the full 5-hydroxytryptophan + Tranylcypromine interactionL-theanineSerotonergic Drugs Minor
Interaction Summary
Clinical studies regarding the effects of L-theanine on serotonin levels are conflicting.
Read the full L-theanine + Tranylcypromine interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with Sleep Advance — through 1 ingredient. Tap an ingredient for the detail:
MelatoninImmunosuppressants Moderate
Interaction Summary
Theoretically, melatonin might interfere with immunosuppressive therapy.
Read the full Melatonin + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with Sleep Advance — through 2 ingredients. Tap an ingredient for the detail:
Phellodendron, PowderCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, phellodendron might increase serum levels of drugs metabolized by CYP3A4.
Read the full Phellodendron, Powder + Ado-trastuzumab Emtansine interactionMelatoninCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, melatonin might increase levels of drugs metabolized by CYP3A4.
Read the full Melatonin + Ado-trastuzumab Emtansine interactionAbciximabReoPro
How Abciximab interacts with Sleep Advance — through 3 ingredients. Tap an ingredient for the detail:
MelatoninAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, melatonin may have anticoagulant effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Melatonin + Abciximab interactionPhellodendron, PowderAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, phellodendron might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Phellodendron, Powder + Abciximab interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with Sleep Advance — through 2 ingredients. Tap an ingredient for the detail:
Phellodendron, PowderCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, phellodendron might increase serum levels of drugs metabolized by CYP3A4.
Read the full Phellodendron, Powder + Abemaciclib interactionMelatoninCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, melatonin might increase levels of drugs metabolized by CYP3A4.
Read the full Melatonin + Abemaciclib interactionAbiraterone
How Abiraterone interacts with Sleep Advance — through 2 ingredients. Tap an ingredient for the detail:
Phellodendron, PowderCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, phellodendron might increase serum levels of drugs metabolized by CYP3A4.
Read the full Phellodendron, Powder + Abiraterone interactionMelatoninCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, melatonin might increase levels of drugs metabolized by CYP3A4.
Read the full Melatonin + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with Sleep Advance — through 2 ingredients. Tap an ingredient for the detail:
Phellodendron, PowderCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, phellodendron might increase serum levels of drugs metabolized by CYP3A4.
Read the full Phellodendron, Powder + Abiraterone Acetate interactionMelatoninCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, melatonin might increase levels of drugs metabolized by CYP3A4.
Read the full Melatonin + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with Sleep Advance — through 3 ingredients. Tap an ingredient for the detail:
Phellodendron, PowderAnticoagulant/antiplatelet Drugs, Cytochrome P450 2c9 (cyp2c9) Substrates Moderate
Interaction Summary
Theoretically, phellodendron might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Phellodendron, Powder + Abrocitinib interactionMelatoninCytochrome P450 2c19 (cyp2c19) Substrates, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, melatonin might increase levels of drugs metabolized by CYP2C19.
Read the full Melatonin + Abrocitinib interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with Sleep Advance — through 2 ingredients. Tap an ingredient for the detail:
Phellodendron, PowderCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, phellodendron might increase serum levels of drugs metabolized by CYP3A4.
Read the full Phellodendron, Powder + Acalabrutinib interactionMelatoninCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, melatonin might increase levels of drugs metabolized by CYP3A4.
Read the full Melatonin + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Sleep Advance — through 3 ingredients. Tap an ingredient for the detail:
Phellodendron, PowderAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, phellodendron may increase the risk of hypoglycemia when taken with antidiabetes drugs.
Read the full Phellodendron, Powder + Acarbose interactionMelatoninAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking melatonin with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Melatonin + Acarbose interactionMucuna Pruriens Seed ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, concomitant use of cowhage and antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Mucuna Pruriens Seed Extract + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Sleep Advance — through 4 ingredients. Tap an ingredient for the detail:
L-theanineAntihypertensive Drugs Moderate
Interaction Summary
Theanine might lower blood pressure, potentiating the effects of antihypertensive drugs.
Read the full L-theanine + Acebutolol interactionPhellodendron, PowderAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, phellodendron might have additive effects with antihypertensive drugs.
Read the full Phellodendron, Powder + Acebutolol interactionMelatoninAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking melatonin with antihypertensive drugs might increase the risk of hypotension or hypertension.
Read the full Melatonin + Acebutolol interactionGamma-aminobutyric AcidAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking GABA with antihypertensive drugs might increase the risk of hypotension.
Read the full Gamma-aminobutyric Acid + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Sleep Advance — through 3 ingredients. Tap an ingredient for the detail:
Phellodendron, PowderAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, phellodendron might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Read the full Phellodendron, Powder + Acenocoumarol interactionMelatoninAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, melatonin may have anticoagulant effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Melatonin + Acenocoumarol interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Acenocoumarol interactionAcepromazineAtravet
How Acepromazine interacts with Sleep Advance — through 6 ingredients. Tap an ingredient for the detail:
Mucuna Pruriens Seed ExtractAntipsychotic Drugs Moderate
Interaction Summary
Theoretically, use of cowhage might decrease the clinical effects of antipsychotic drugs.
Read the full Mucuna Pruriens Seed Extract + Acepromazine interactionPhellodendron, PowderCns Depressants Moderate
Interaction Summary
Theoretically, phellodendron might increase the sedative effects of CNS depressants.
Read the full Phellodendron, Powder + Acepromazine interaction5-hydroxytryptophanCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use of 5-HTP with medications that cause sedation might have additive effects.
Read the full 5-hydroxytryptophan + Acepromazine interactionMelatoninCns Depressants Moderate
Interaction Summary
Theoretically, taking melatonin might increase the sedative effects of CNS depressants.
Read the full Melatonin + Acepromazine interactionL-theanineCns Depressants Minor
Interaction Summary
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants.
Read the full L-theanine + Acepromazine interactionGamma-aminobutyric AcidCns Depressants Minor
Interaction Summary
Theoretically, GABA might have additive sedative effects when used in conjunction with CNS depressants.
Read the full Gamma-aminobutyric Acid + Acepromazine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Sleep Advance with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Melatonin
Anticoagulant/Antiplatelet Drugs
Theoretically, melatonin may have anticoagulant effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
There are isolated case reports of minor bleeding and decreased prothrombin activity in people taking melatonin with warfarin (Coumadin). The mechanism, if any, of this interaction is unknown. Taking melatonin orally seems to decrease coagulation activity within one hour of dosing in healthy men.
Anticonvulsants
Theoretically, melatonin may reduce the effects of anticonvulsants. Some clinical research suggests that melatonin may increase the frequency of seizures in certain patients, particularly children with neurological impairment.
Antidiabetes Drugs
Theoretically, taking melatonin with antidiabetes drugs might increase the risk of hypoglycemia.
Some clinical research shows that melatonin reduces levels of fasting blood glucose and improves glycemic control. However, other research suggests that melatonin might impair glucose utilization and increase insulin resistance, while other research has found no effect on glucose levels. Until more is known, use melatonin cautiously in combination with antidiabetes drugs.
Antihypertensive Drugs
Theoretically, taking melatonin with antihypertensive drugs might increase the risk of hypotension or hypertension.
Some clinical research suggests that taking melatonin decreases blood pressure in healthy adults. Also, melatonin seems to lower systolic and diastolic blood pressure in individuals with high blood pressure at nighttime or untreated essential hypertension. However, melatonin seems to worsen blood pressure in patients who are taking antihypertensive medications. Immediate-release melatonin 5 mg at night in combination with nifedipine GITS (Procardia XL) increases systolic blood pressure an average of 6.5 mmHg, diastolic blood pressure by an average of 4.9 mmHg, and heart rate by 3.9 bpm. Also, results from animal research suggest that melatonin reduces the effectiveness of certain antihypertensive drugs, including methoxamine and clonidine.
Caffeine
Theoretically, taking caffeine with melatonin might increase levels of melatonin.
Some evidence suggests that caffeine consumption can decrease endogenous melatonin levels, while other evidence suggests that caffeine increases endogenous melatonin levels. When administered in combination with melatonin supplements, caffeine seems to increase melatonin effects and levels. The reason for this discrepancy is not completely clear. Part of the discrepancy may result from the fact that caffeine can inhibit melatonin synthesis as well as inhibit melatonin metabolism. By functioning as an adenosine receptor antagonist, caffeine may indirectly inhibit the synthesis of melatonin. Conversely, because melatonin and caffeine are both metabolized by cytochrome P450 1A2 (CYP1A2) enzyme, concomitant use of melatonin and caffeine may reduce the metabolism of melatonin, resulting in higher serum levels.
Cns Depressants
Theoretically, taking melatonin might increase the sedative effects of CNS depressants.
Melatonin has sedative effects. Theoretically, concomitant use of melatonin with alcohol, benzodiazepines, or other sedative drugs might cause additive sedation.
Contraceptive Drugs
Theoretically, taking contraceptive drugs with melatonin might increase the effects and adverse effects of melatonin.
Contraceptive drugs can increase the levels of endogenous melatonin. Theoretically, these drugs may increase the effects and adverse effects of oral melatonin.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, melatonin might increase levels of drugs metabolized by CYP1A2. Also, other CYP1A2 substrates might decrease the metabolism of melatonin, increasing melatonin levels.
Melatonin is metabolized in the liver primarily by the CYP2C19 and CYP1A2 enzymes. Theoretically, combined administration of melatonin with drugs metabolized by the CYP1A2 enzyme might reduce the metabolism of these drugs, resulting in increased serum levels. Conversely, some drugs metabolized by CYP1A2 may inhibit the metabolism of melatonin, resulting in increased serum levels of melatonin. Until more is known, use melatonin cautiously in patients taking drugs metabolized by these enzymes.
Cytochrome P450 2C19 (Cyp2C19) Substrates
Theoretically, melatonin might increase levels of drugs metabolized by CYP2C19. Also, other CYP2C19 substrates might decrease the metabolism of melatonin, increasing melatonin levels.
Melatonin is metabolized in the liver primarily by the CYP2C19 and CYP1A2 enzymes. Theoretically, combined administration of melatonin with certain drugs metabolized by the CYP2C19 enzyme may reduce the metabolism of these drugs, resulting in increased serum levels. Conversely, some drugs metabolized by CYP2C19 may inhibit the metabolism of melatonin, resulting in increased serum levels of melatonin. Until more is known, use melatonin cautiously in patients taking drugs metabolized by these enzymes.
Fluvoxamine (Luvox)
Theoretically, taking fluvoxamine with melatonin might increase levels of melatonin.
Fluvoxamine can significantly increase melatonin levels. In some cases, fluvoxamine might increase bioavailability of exogenously administered melatonin by up to 20 times. Some researchers think this might be a beneficial interaction and be potentially useful for cases of refractory insomnia. However, this interaction might also cause unwanted excessive drowsiness and possibly other adverse effects. Fluvoxamine is known to increase endogenous melatonin secretion. It seems to increase serum levels of exogenously administered melatonin possibly by decreasing melatonin metabolism by inhibiting cytochrome P450 (CYP450) 1A2 and 2C19 or by inhibiting melatonin elimination. This effect has been found in healthy people taking fluvoxamine 50-75 mg and melatonin 5 mg.
Immunosuppressants
Theoretically, melatonin might interfere with immunosuppressive therapy.
Melatonin can stimulate immune function. Theoretically, melatonin might interfere with immunosuppressive therapy.
Methamphetamine (Desoxyn)
Theoretically, taking melatonin with methamphetamine may increase the adverse effects of methamphetamine.
Animal research suggests that melatonin exacerbates the adverse effects of methamphetamine, resulting in greater depression of tryptophan hydroxylase (TPH) and tyrosine hydroxylase (TH) activity, as well as a significant reduction in dopamine levels. This has not been shown in humans.
Nifedipine Gits (Procardia Xl)
Theoretically, taking melatonin with extended release nifedipine reduces the effects of nifedipine.
Melatonin can decrease the effectiveness of extended release nifedipine (GITS). Immediate-release melatonin 5 mg at night in combination with nifedipine GITS 30-60 mg daily increases systolic and blood pressure by an average of 6.5 mmHg and 4.9 mmHg, respectively. Concomitant use with melatonin also increases heart rate by 3.9 bpm. The mechanism of this interaction is not known.
Seizure Threshold Lowering Drugs
Theoretically, taking melatonin with drugs that lower the seizure threshold might increase the risk of seizure activity.
Some clinical evidence suggests that melatonin may increase the frequency of seizures in certain patients, particularly children with neurological disabilities.
Warfarin (Coumadin)
Theoretically, melatonin may have antiplatelet effects and may increase the risk of bleeding with warfarin.
Three cases of increased prothrombin time have been reported for patients aged 48-72 years who took melatonin orally in combination with warfarin. However, three cases of decreased prothrombin time have also been reported for patients aged 51-84 years who took melatonin orally in combination with warfarin. Until more is known, use melatonin cautiously in patients taking warfarin.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, melatonin might increase levels of drugs metabolized by CYP2D6.
Laboratory research suggests that certain lots of melatonin inhibit CYP2D6. Theoretically, combined administration of melatonin with certain drugs metabolized by the CYP2D6 enzyme may reduce the metabolism of these drugs, resulting in increased serum levels. Until more is known, use melatonin cautiously in patients taking drugs metabolized by these enzymes.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, melatonin might increase levels of drugs metabolized by CYP3A4.
Laboratory research shows that certain lots of melatonin inhibit CYP3A4. Theoretically, combined administration of melatonin with certain drugs metabolized by CYP3A4 may reduce the metabolism of these drugs, resulting in increased serum levels. Until more is known, use melatonin cautiously in patients taking drugs metabolized by these enzymes.
Flumazenil (Romazicon)
Theoretically, taking flumazenil with melatonin might reduce the effects of melatonin.
Animal research shows that flumazenil may inhibit the effect of melatonin.
Phellodendron, Powder
Anticoagulant/Antiplatelet Drugs
Theoretically, phellodendron might increase the risk of bleeding when used with anticoagulant or antiplatelet drugs.
Phellodendron contains berberine. In vitro and in vivo research suggest that berberine can inhibit platelet aggregation. Theoretically, phellodendron might also inhibit platelet aggregation.
Antidiabetes Drugs
Theoretically, phellodendron may increase the risk of hypoglycemia when taken with antidiabetes drugs.
Phellodendron contains berberine. Clinical research shows that berberine may lower blood glucose levels. Theoretically, phellodendron might also lower blood glucose levels.
Antihypertensive Drugs
Theoretically, phellodendron might have additive effects with antihypertensive drugs.
Phellodendron contains berberine. Animal research suggests that berberine can have hypotensive effects. Also, a clinical study suggests that taking berberine in combination with amlodipine can lower systolic and diastolic blood pressure when compared with amlodipine alone. Theoretically, phellodendron might also reduce blood pressure.
Cns Depressants
Theoretically, phellodendron might increase the sedative effects of CNS depressants.
Phellodendron contains berberine. Animal research suggests that berberine may have sedative effects. Theoretically, phellodendron might also have CNS depressants effects.
Cyclosporine (Neoral, Sandimmune)
Theoretically, phellodendron might increase blood levels of cyclosporine.
Phellodendron contains berberine. Preliminary clinical research shows that berberine can reduce metabolism of cyclosporine and increase serum levels, likely through inhibition of cytochrome P450 3A4 (CYP3A4), which metabolizes cyclosporine. Theoretically, phellodendron might also reduce the metabolism of cyclosporine.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, phellodendron might increase serum levels of drugs metabolized by CYP2C9.
Phellodendron contains berberine. Preliminary clinical research shows that berberine can inhibit CYP2C9. Theoretically, phellodendron might also inhibit CYP2C9.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, phellodendron might increase serum levels of drugs metabolized by CYP2D6.
Phellodendron contains berberine. In vitro research and preliminary clinical evidence show that berberine can inhibit CYP2D6. Theoretically, phellodendron might also inhibit CYP2D6.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, phellodendron might increase serum levels of drugs metabolized by CYP3A4.
Phellodendron contains berberine. In vitro research and preliminary clinical research show that berberine moderately inhibits CYP3A4. Theoretically, phellodendron might also inhibit CYP3A4.
Dextromethorphan (Robitussin Dm, Others)
Theoretically, phellodendron may increase serum levels of dextromethorphan.
Phellodendron contains berberine. Preliminary clinical research shows that berberine can inhibit cytochrome P450 2D6 (CYP2D6) activity and reduce the metabolism of dextromethorphan. Theoretically, phellodendron may also inhibit the metabolism of dextromethorphan.
Losartan (Cozaar)
Theoretically, phellodendron might reduce the therapeutic effects of losartan by decreasing its conversion to its active form.
Phellodendron contains berberine. Preliminary clinical research suggests that berberine can inhibit cytochrome P450 2C9 (CYP2C9) activity and reduce metabolism of losartan. Theoretically, phellodendron might also inhibit the metabolism of losartan.
Metformin (Glucophage)
Theoretically, phellodendron might increase the therapeutic and adverse effects of metformin.
Phellodendron contains berberine. In vitro and animal studies show that berberine can increase the systemic exposure and half-life of metformin, potentially increasing metformin's effects and side effects. This interaction seems to be most apparent when berberine is administered 2 hours prior to metformin. Taking berberine and metformin at the same time does not appear to increase systemic exposure to metformin. It is unclear if phellodendron might have this same effect.
Midazolam (Versed)
Theoretically, phellodendron might reduce metabolism of midazolam, which might increase the risk of severe adverse effects.
Phellodendron contains berberine. Preliminary clinical research shows that berberine can inhibit cytochrome P450 3A4 (CYP3A4) activity and reduce metabolism of midazolam. Theoretically, phellodendron might also inhibit the metabolism of midazolam.
Pentobarbital (Nembutal)
Theoretically, phellodendron might increase the sedative effect of pentobarbital.
Phellodendron contains berberine. Animal research shows that berberine can prolong pentobarbital-induced sleeping time. Theoretically, phellodendron might increase the sedative effects of pentobarbital.
Tacrolimus (Prograf)
Theoretically, phellodendron might increase blood levels of tacrolimus.
Phellodendron contains berberine. In a 16-year-old patient with idiopathic nephrotic syndrome who was being treated with tacrolimus 6.5 mg twice daily, intake of berberine 200 mg three times daily increased the blood concentration of tacrolimus from 8 to 22 ng/mL. Following a reduction of the tacrolimus dose to 3 mg daily, blood levels of tacrolimus decreased to 12 ng/mL. It is unclear if phellodendron might have this same effect.
L-Theanine
Antihypertensive Drugs
Theanine might lower blood pressure, potentiating the effects of antihypertensive drugs.
Animal research shows that theanine can lower blood pressure in spontaneously hypertensive animals. Theoretically, concomitant use of theanine and antihypertensive drugs might potentiate the antihypertensive activity.
Cns Depressants
Theoretically, theanine might have additive sedative effects when used in conjunction with CNS depressants. However, it is unclear if this concern is clinically relevant.
Theoretically, theanine may compete with glutamate and/or increase plasma gamma-aminobutyric acid (GABA) levels, which could cause CNS depression. In one clinical study, some subjects taking oral theanine reported drowsiness.
Serotonergic Drugs
Clinical studies regarding the effects of L-theanine on serotonin levels are conflicting. Some studies suggest it can increase serotonin levels in the brain while others report that it may decrease them. Nevertheless, there have been no reports of l-theanine being a causative agent in serotonergic-related side effects or serotonin syndrome.
Gamma-Aminobutyric Acid
Antihypertensive Drugs
Theoretically, taking GABA with antihypertensive drugs might increase the risk of hypotension.
Some clinical research shows that GABA can decrease blood pressure in patients with hypertension.
Cns Depressants
Theoretically, GABA might have additive sedative effects when used in conjunction with CNS depressants. However, it is unclear if this concern is clinically relevant.
Endogenous GABA has well-established relaxant effects and GABA(A) receptors have an established physiological role in sleep. However, the effects of GABA supplements are unclear, as it is unknown whether exogenous GABA crosses the blood-brain barrier. Although there have been limited reports of drowsiness or tiredness with GABA supplements, these effects have not been widely reported in clinical studies. Additionally, intravenous GABA 0.1-1 mg/kg has been shown to induce anxiety in a dose-dependent manner.
5-Hydroxytryptophan
Carbidopa (Lodosyn)
Combining 5-HTP and carbidopa can increase the risk of serotonergic side effects.
Carbidopa is sometimes used with 5-HTP to minimize peripheral 5-HTP metabolism and boost the amount that reaches the brain. However, this combination might also increase the risk of some side effects including hypomania, restlessness, rapid speech, anxiety, insomnia, and aggressiveness. Combining carbidopa and 5-HTP might also increase the risk of scleroderma-like skin changes due to elevated serotonin levels.
Cns Depressants
Theoretically, concomitant use of 5-HTP with medications that cause sedation might have additive effects.
In clinical trials, 5-HTP has been associated with drowsiness and somnolence.
Serotonergic Drugs
Combining serotonergic drugs with 5-HTP might cause additive serotonergic effects.
5-HTP can increase serotonin levels and cause serotonergic effects. Theoretically, combining serotonergic drugs with 5-HTP might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders. However, serotonin syndrome with 5-HTP has not yet been reported in humans. Monitor patients for signs of serotonin syndrome and other serotonergic side effects if using 5-HTP with serotonergic drugs.
Magnesium
Levodopa/Carbidopa (Sinemet)
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Clinical research in healthy volunteers shows that taking magnesium oxide 1000 mg with levodopa 100 mg/carbidopa 10 mg reduces the area under the curve (AUC) of levodopa by 35% and of carbidopa by 81%. In vitro and animal research shows that magnesium produces an alkaline environment in the digestive tract, which might lead to degradation and reduced bioavailability of levodopa/carbidopa.
Aminoglycoside Antibiotics
Concomitant use of aminoglycoside antibiotics and magnesium can increase the risk for neuromuscular weakness.
Both aminoglycosides and magnesium reduce presynaptic acetylcholine release, which can lead to neuromuscular blockade and possible paralysis. This is most likely to occur with high doses of magnesium given intravenously.
Antacids
Use of acid reducers may reduce the laxative effect of magnesium oxide.
A retrospective analysis shows that, in the presence of H2 receptor antagonists (H2RAs) or proton pump inhibitors (PPIs), a higher dose of magnesium oxide is needed for a laxative effect. This may also occur with antacids. Under acidic conditions, magnesium oxide is converted to magnesium chloride and then to magnesium bicarbonate, which has an osmotic laxative effect. By reducing acidity, antacids may reduce the conversion of magnesium oxide to the active bicarbonate salt.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after magnesium containing products.
Bisphosphonates
Magnesium can decrease absorption of bisphosphonates.
Cations, including magnesium, can decrease bisphosphonate absorption. Advise patients to separate doses of magnesium and these drugs by at least 2 hours.
Calcium Channel Blockers
Magnesium can have additive effects with calcium channel blockers, although evidence is conflicting.
Magnesium inhibits calcium entry into smooth muscle cells and may therefore have additive effects with calcium channel blockers. Severe hypotension and neuromuscular blockades may occur when nifedipine is used with intravenous magnesium, although some contradictory evidence suggests that concurrent use of magnesium with nifedipine does not increase the risk of neuromuscular weakness. High doses of magnesium could theoretically have additive effects with other calcium channel blockers.
Digoxin
Magnesium salts may reduce absorption of digoxin.
Clinical evidence suggests that treatment with oral magnesium hydroxide or magnesium trisilicate reduces absorption of digoxin from the intestines. This may reduce the blood levels of digoxin and decrease its therapeutic effects.
Potassium-Sparing Diuretics
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Potassium-sparing diuretics also have magnesium-sparing properties, which can counteract the magnesium losses associated with loop and thiazide diuretics. Theoretically, increased magnesium levels could result from concomitant use of potassium-sparing diuretics and magnesium supplements.
Quinolone Antibiotics
Magnesium decreases absorption of quinolones.
Magnesium can form insoluble complexes with quinolones and decrease their absorption. Advise patients to take these drugs at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Skeletal Muscle Relaxants
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Parenteral magnesium shortens the time to onset of skeletal muscle relaxants by about 1 minute and prolongs the duration of action by about 2 minutes. Magnesium potentiates the effects of skeletal muscle relaxants by decreasing calcium-mediated release of acetylcholine from presynaptic nerve terminals, reducing postsynaptic sensitivity to acetylcholine, and having a direct effect on the membrane potential of myocytes. Magnesium also has vasodilatory actions and increases cardiac output, allowing a greater amount of muscle relaxant to reach the motor end plate. A clinical study found that low-dose rocuronium (0.45 mg/kg), when given after administration of magnesium 30 mg/kg over 10 minutes, has an accelerated onset of effect, which matches the onset of effect seen with a full-dose rocuronium regimen (0.6 mg/kg). In another clinical study, onset times for rocuronium doses of 0.3, 0.6, and 1.2 mg/kg were 86, 76, and 50 seconds, respectively, when given alone, but were reduced to 66, 44, and 38 seconds, respectively, when the doses were given after a 15-minute infusion of magnesium sulfate 60 mg/kg. Giving intraoperative intravenous magnesium sulfate, 50 mg/kg loading dose followed by 15 mg/kg/hour, reduces the onset time of rocuronium, enhances its clinical effects, reduces the dose of intraoperative opiates, and prolongs the spontaneous recovery time. It does not affect the activity of subsequently administered neostigmine.
Sulfonylureas
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Clinical research shows that administration of magnesium hydroxide with glyburide increases glyburide absorption, increases maximal insulin response by 35-fold, and increases the risk of hypoglycemia, when compared with glyburide alone. A similar interaction occurs between magnesium hydroxide and glipizide. The mechanism of this effect appears to be related to the elevation of gastrointestinal pH by magnesium-based antacids, increasing solubility and enhancing absorption of sulfonylureas.
Tetracycline Antibiotics
Magnesium decreases absorption of tetracyclines.
Magnesium can form insoluble complexes with tetracyclines in the gut and decrease their absorption and antibacterial activity. Advise patients to take these drugs 1 hour before or 2 hours after magnesium supplements.
Anticoagulant/Antiplatelet Drugs
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
In vitro evidence shows that magnesium sulfate inhibits platelet aggregation, even at low concentrations. Some preliminary clinical evidence shows that infusion of magnesium sulfate increases bleeding time by 48% and reduces platelet activity. However, other clinical research shows that magnesium does not affect platelet aggregation, although inhibition of platelet-dependent thrombosis can occur.
Gabapentin (Neurontin)
Gabapentin absorption can be decreased by magnesium.
Clinical research shows that giving magnesium oxide orally along with gabapentin decreases the maximum plasma concentration of gabapentin by 33%, time to maximum concentration by 36%, and area under the curve by 43%. Advise patients to take gabapentin at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Sevelamer (Renagel, Renvela)
Sevelamer may increase serum magnesium levels.
In patients on hemodialysis, sevelamer use was associated with a 0.28 mg/dL increase in serum magnesium. The mechanism of this interaction remains unclear.
Mucuna pruriens Seed Extract
Levodopa
Concomitant use can increase the risk of levodopa-related adverse effects.
Cowhage contains levodopa. Some cowhage products have been standardized to contain 75-400 mg of levodopa per dose.
Methyldopa (Aldomet)
Theoretically, concomitant use of cowhage and methyldopa might increase the risk of hypotension.
Cowhage contains levodopa. Use of levodopa with methyldopa might cause additive hypotension. In addition, methyldopa may inhibit peripheral decarboxylation of levodopa and increase levodopa levels in the central nervous system; avoid using.
Monoamine Oxidase Inhibitors (Maois)
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Cowhage contains levodopa. Use of levodopa with non-selective MAOIs might cause hypertensive crisis. However, this interaction has not been reported with MAO-B selective inhibitors such as selegiline.
Anesthesia
Theoretically, concomitant use of cowhage and anesthesia might increase the risk of arrhythmias.
Cowhage contains levodopa. Use of levodopa with cyclopropane or halogenated hydrocarbon anesthesia has led to arrhythmias. Other anesthetics have not been implicated. Use other anesthetics in patients taking cowhage or tell patients to stop taking cowhage at least 2 weeks before surgery.
Antidiabetes Drugs
Theoretically, concomitant use of cowhage and antidiabetes drugs might increase the risk of hypoglycemia.
Animal research shows that cowhage might have hypoglycemic effects.
Antipsychotic Drugs
Theoretically, use of cowhage might decrease the clinical effects of antipsychotic drugs.
Cowhage contains levodopa. Use of levodopa might counteract the antidopaminergic effects of antipsychotic medications.
Guanethidine (Ismelin)
Theoretically, concomitant use of cowhage and guanethidine might increase the risk of hypotension.
Cowhage contains levodopa. Use of levodopa with guanethidine might cause additive hypotension; avoid using.
Tricyclic Antidepressants (Tcas)
Theoretically, use of TCAs might reduce the levels and clinical effects of cowhage.
Cowhage contains levodopa. Use of TCAs might reduce the absorption of levodopa. Some case reports describe patients that developed hypertension and dyskinesia when taking both levodopa and TCAs.
Brand information
Manufacturer and brand details for Sleep Advance, from the product label.
Logos Nutritionals
See all Logos Nutritionals products- Name
- Logos Nutritionals, LLC.
- Street Address
- 912 Killian Hill Road SW, Ste. 202-O
- City
- Lilburn
- State
- GA
- ZipCode
- 30047
- Phone Number
- 800-556-5530
- Web Address
- www.logosnutritionals.com
Sleep Advance by Logos Nutritionals: Common Questions
Does Sleep Advance by Logos Nutritionals interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take Sleep Advance if I'm pregnant?
Is it safe to take Sleep Advance while breastfeeding?
What are the most common side effects of Sleep Advance?
Does Sleep Advance actually help you sleep?
What is Mucuna pruriens, and why is it in a sleep product?
Why should I be careful with this product if I take blood pressure medication?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Sleep Advance is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Sleep Advance’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Melatonin
Interacts with 1,461 drugsMelatonin is a hormone your body makes naturally to help control your sleep-wake cycle, and the supplement form is widely used to help with sleep timing problems and jet lag. The evidence is...
Read the full Melatonin monograph → Herb & supplement monographTheanine
Interacts with 565 drugsTheanine (usually L-theanine) is an amino acid found naturally in tea leaves that many people take to feel calmer and less stressed without strong drowsiness. Early research suggests it may...
Read the full Theanine monograph → Herb & supplement monograph5-htp
Interacts with 398 drugs5-HTP is a compound your body uses to make serotonin, and people take it as a supplement hoping to improve mood, sleep, and headaches. Some early research is promising, but the overall evide...
Read the full 5-htp monograph → Herb & supplement monographMagnesium
Interacts with 295 drugsMagnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preventing or correcting deficiency. Some othe...
Read the full Magnesium monograph → Herb & supplement monographCowhage
Interacts with 193 drugsCowhage (Mucuna pruriens) is a tropical legume best known as a natural source of L-dopa, the compound the body turns into dopamine. It is most studied for Parkinson's disease symptoms and ma...
Read the full Cowhage monograph → Herb & supplement monographPhellodendron
Interacts with 1,160 drugsPhellodendron is a traditional Chinese medicine bark (Huang Bai) that contains berberine and other plant compounds with antimicrobial and anti-inflammatory activity in lab studies. Human evi...
Read the full Phellodendron monograph → Herb & supplement monographGamma-aminobutyric Acid (gaba)
Interacts with 419 drugsGABA is a calming chemical messenger (neurotransmitter) that your body makes on its own, and it is sold as a supplement for stress, anxiety, and sleep. The science behind oral GABA supplemen...
Read the full Gamma-aminobutyric Acid (gaba) monograph →Sources & How We Checked
Sleep Advance's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 284 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Melatonin 118 references
- Voordouw BC, Euser R, Verdonk RE, et al. Melatonin and melatonin-progestin combinations alter pituitary-ovarian function in women and can inhibit ovulation. J Clin Endocrinol Metab 1992;74:108-17. DOI
- Ellis CM, Lemmens G, Parkes JD. Melatonin and insomnia. J Sleep Res 1996;5:61-5. PubMed
- Petrie K, Dawson AG, Thompson L, Brook R. A double-blind trial of melatonin as a treatment for jet lag in international cabin crew. Biol Psychiatr 1993;33:526-30. PubMed
- Claustrat B, Brun J, David M, et al. Melatonin and jet lag: confirmatory result using a simplified protocol. Biol Psychiatr 1992;32:705-11.
- Fauteck J, Schmidt H, Lerchl A, et al. Melatonin in epilepsy: first results of replacement therapy and first clinical results. Biol Signals Recept 1999;8:105-10. PubMed
- Arangino S, Cagnacci A, Angiolucci M, et al. Effects of melatonin on vascular reactivity, catecholamine levels, and blood pressure in healthy men. Am J Cardiol 1999;83:1417-9. PubMed
- Pierce A. The American Pharmaceutical Association Practical Guide to Natural Medicines. New York: The Stonesong Press, 1999:19.
- Lancioni GE, O'Reilly MF, Basili G. Review of strategies for treating sleep problems in persons with severe or profound mental retardation or multiple handicaps. Am J Ment Retard 1999;104:170-86. PubMed
- Carman JS, Post RM, Buswell R, et al. Negative effects of melatonin on depression. Am J Psychiatry 1976;133:1181-1186. PubMed
- Hartter S, Grozinger M, Weigmann H, et al. Increased bioavailability of oral melatonin after fluvoxamine coadministration. Clin Pharmacol Ther 2000;67:1-6.
- Fetrow CW, Avila JR. Professional's Handbook of Complementary & Alternative Medicines. 1st ed. Springhouse, PA: Springhouse Corp., 1999.
- Lusardi P, et al. Cardiovascular effects of melatonin in hypertensive patients well controlled by nifedipine: a 24-hour study. Br J Clin Pharmacol 2000;49:423-7. PubMed
- von Bahr C, Ursing C, Yasui N, et al. Fluvoxamine but not citalopram increases serum melatonin in healthy subjects – an indication that cytochrome P450 CYP1A2 and CYP2C19 hydroxylate melatonin. Eur J Clin Pharmacol 2000;56:123-7.
- Grozinger M, Hartter S, Wang X, et al. Fluvoxamine strongly inhibits melatonin metabolism in a patient with low-amplitude melatonin profile. Arch Gen Psychiatry 2000 Aug;57:812-3. PubMed
- Lissoni P, Barni S, Mandala M, et al. Decreased toxicity and increased efficacy of cancer chemotherapy using the pineal hormone melatonin in metastatic solic tumor patients with poor clinical status. Eur J Cancer 1999;35:1688-92.
- Sheldon SH. Pro-convulsant effects of oral melatonin in neurologically disabled children. Lancet 1998;351:1254. PubMed
- Hartter S, Grozinger M, Weigmann H, et al. Increased bioavailability of oral melatonin after fluvoxamine coadministration. Clin Pharmacol Ther 2000;67:1-6.
- Wright KP Jr, Myers BL, Plenzler SC, et al. Acute effects of bright light and caffeine on nighttime melatonin and temperature levels in women taking and not taking oral contraceptives. Brain Res 2000;873:310-7.
- Herxheimer A, Petrie KJ. Melatonin for preventing and treating jet lag. Cochrane Database Syst Rev 2001;(1):CD001520.
- Briggs, Freeman, Yafee. Update Drugs in Pregnancy and Lactation. Lippincott Williams & Wilkins, 2001.
- Suhner A, Schlagenhauf P, Johnson R, et al. Comparative study to determine the optimal melatonin dosage form for the alleviation of jet lag. Chronobiol Int 1998;15:655-66. PubMed
- Herxheimer A, Petrie KJ. Melatonin for the prevention and treatment of jet lag. Cochrane Database Syst Rev 2002;2:CD001520. PubMed
- Munoz-Hoyos A, Sanchez-Forte M, Molina-Carballo A, et al. Melatonin's role as an anticonvulsant and neuronal protector: experimental and clinical evidence. J Child Neurol 1998;13:501-9.. PubMed
- Sandyk R, Tsagas N, Anninos PA. Melatonin as a proconvulsive hormone in humans. Int J Neurosci 1992;63:125-35.. PubMed
- Golombek DA, Escolar E, Burin LJ, et al. Chronopharmacology of melatonin: inhibition by benzodiazepine antagonism. Chronobiol Int 1992;9:124-31.. PubMed
- Smits MG, Nagtegaal EE, van der Heijden J, et al. Melatonin for chronic sleep onset insomnia in children: a randomized placebo-controlled trial. J Child Neurol 2001;16:86-92.. PubMed
- Cagnacci A, Arangino S, Renzi A, et al. Influence of melatonin administration on glucose tolerance and insulin sensitivity of postmenopausal women. Clin Endocrinol (Oxf) 2001;54:339-46.. PubMed
- Williamson BL, Tomlinson AJ, Naylor S, Gleich GJ. Contaminants in commercial preparations of melatonin. Mayo Clin Proc 1997;72:1094-5. PubMed
- Williamson BL, Tomlinson AJ, Mishra PK, et al. Structural characterization of contaminants found in commercial preparations of melatonin: similarities to case-related compounds from L-tryptophan associated with eosinophilia-myalgia syndrome. Chem Res To
- Stewart LS. Endogenous melatonin and epileptogenesis: facts and hypothesis. Int J Neurosci 2001;107:77-85.. PubMed
- Molina-Carballo A, Munoz-Hoyos A, Reiter RJ, et al. Utility of high doses of melatonin as adjunctive anticonvulsant therapy in a child with severe myoclonic epilepsy: two years' experience. J Pineal Res 1997;23:97-105.. PubMed
- Tjon Pian Gi CV, Broeren JP, Starreveld JS, A Versteegh FG. Melatonin for treatment of sleeping disorders in children with attention deficit/hyperactivity disorder: a preliminary open label study. Eur J Pediatr 2003;162:554-5. PubMed
- Secreto G, Chiechi LM, Amadori A, et al. Soy isoflavones and melatonin for the relief of climacteric symptoms: a multicenter, double-blind, randomized study. Maturitas 2004;47:11-20. PubMed
- Weiss MD, Wasdell MB, Bomben MM, et al. Sleep hygiene and melatonin treatment for children and adolescents with ADHD and initial insomnia. J Am Acad Child Adolesc Psychiatry 2006;45:512-9. DOI
- Saha L, Malhotra S, Rana S, et al. A preliminary study of melatonin in irritable bowel syndrome. J Clin Gastroenterol 2007;41:29-32. PubMed
- Hussain, SA, Khadim, HM, Khalaf, BH, et al. Effects of melatonin and zinc on glycemic control in type 2 diabetic patients poorly controlled with metformin. Saudi Med J 2006;27:1483-8. DOI
- Kadhim, HM, Ismail, SH, Hussein, KI, et al. Effects of melatonin and zinc on lipid profile and renal function in type 2 diabetic patients poorly controlled with metformin. J Pineal Res 2006;41:189-93. PubMed
- Mutluay R. Elbeg S. Karakus R. et al. The Impact of Melatonin on Glucose Homeostasis. Turkish Journal of Endocrinology and Metabolism 2009;13:52-55.
- Wright KP Jr, Badia P, Myers BL, et al. Caffeine and light effects on nighttime melatonin and temperature levels in sleep-deprived humans. Brain Res. 1997;747(1):78-84. PubMed
- Peuhkuri K, Sihvola N, Korpela R. Dietary factors and fluctuating levels of melatonin. Food Nutr Res. 2012;56. doi: 10.3402/fnr.v56i0.17252. Epub 2012 Jul 20. PubMed
- Gibb JW, Bush L, Hanson GR. Exacerbation of methamphetamine-induced neurochemical deficits by melatonin. J Pharmacol Exp Ther. 1997;283(2):630-5. DOI
- Sunami E, Usuda K, Nishiyama Y, et al. A preliminary study of fluvoxamine maleate on depressive state and serum melatonin levels in patients after cerebral infarction. Intern Med. 2012;51(10):1187-93. PubMed
- Babkoff, H., French, J., Whitmore, J., and Sutherlin, R. Single-dose bright light and/or caffeine effect on nocturnal performance. Aviat.Space Environ.Med. 2002;73(4):341-350.
- Rossignol, D. A. Novel and emerging treatments for autism spectrum disorders: a systematic review. Ann.Clin Psychiatry 2009;21(4):213-236. DOI
- Yeleswaram, K., Vachharajani, N., and Santone, K. Involvement of cytochrome P-450 isozymes in melatonin metabolism and clinical implications. J Pineal Res 1999;26(3):190-191. PubMed
- Jan, J. E., Connolly, M. B., Hamilton, D., Freeman, R. D., and Laudon, M. Melatonin treatment of non-epileptic myoclonus in children. Dev.Med Child Neurol. 1999;41(4):255-259. PubMed
- Edwards, B. J., Atkinson, G., Waterhouse, J., Reilly, T., Godfrey, R., and Budgett, R. Use of melatonin in recovery from jet-lag following an eastward flight across 10 time-zones. Ergonomics 2000;43(10):1501-1513. PubMed
- Cagnacci, A., Arangino, S., Angiolucci, M., Melis, G. B., Facchinetti, F., Malmusi, S., and Volpe, A. Effect of exogenous melatonin on vascular reactivity and nitric oxide in postmenopausal women: role of hormone replacement therapy. Clin Endocrinol (Oxf PubMed
- Wakatsuki, A., Okatani, Y., Ikenoue, N., Kaneda, C., and Fukaya, T. Effects of short-term melatonin administration on lipoprotein metabolism in normolipidemic postmenopausal women. Maturitas 4-20-2001;38(2):171-177. PubMed
- Kitajima, T., Kanbayashi, T., Saitoh, Y., Ogawa, Y., Sugiyama, T., Kaneko, Y., Sasaki, Y., Aizawa, R., and Shimisu, T. The effects of oral melatonin on the autonomic function in healthy subjects. Psychiatry Clin Neurosci. 2001;55(3):299-300. PubMed
- Calvo, J. R., Guerrero, J. M., Osuna, C., Molinero, P., and Carrillo-Vico, A. Melatonin triggers Crohn's disease symptoms. J Pineal Res 2002;32(4):277-278. PubMed
- Luboshitzky, R., Shen-Orr, Z., Nave, R., Lavi, S., and Lavie, P. Melatonin administration alters semen quality in healthy men. J Androl 2002;23(4):572-578. DOI
- Rufo-Campos, M. [Melatonin and epilepsy]. Rev Neurol. 2002;35 Suppl 1:S51-S58.
- Ursing, C., Wikner, J., Brismar, K., and Rojdmark, S. Caffeine raises the serum melatonin level in healthy subjects: an indication of melatonin metabolism by cytochrome P450(CYP)1A2. J.Endocrinol.Invest 2003;26(5):403-406. PubMed
- Smits, M. G., van Stel, H. F., van der, Heijden K., Meijer, A. M., Coenen, A. M., and Kerkhof, G. A. Melatonin improves health status and sleep in children with idiopathic chronic sleep-onset insomnia: a randomized placebo-controlled trial. J Am Acad.Chi PubMed
- Boeve, B. F., Silber, M. H., and Ferman, T. J. Melatonin for treatment of REM sleep behavior disorder in neurologic disorders: results in 14 patients. Sleep Med. 2003;4(4):281-284. PubMed
- Hartter, S., Nordmark, A., Rose, D. M., Bertilsson, L., Tybring, G., and Laine, K. Effects of caffeine intake on the pharmacokinetics of melatonin, a probe drug for CYP1A2 activity. Br.J.Clin.Pharmacol. 2003;56(6):679-682. PubMed
- Scheer, F. A., Van Montfrans, G. A., van Someren, E. J., Mairuhu, G., and Buijs, R. M. Daily nighttime melatonin reduces blood pressure in male patients with essential hypertension. Hypertension 2004;43(2):192-197. PubMed
- Buscemi, N., Vandermeer, B., Pandya, R., Hooton, N., Tjosvold, L., Hartling, L., Baker, G., Vohra, S., and Klassen, T. Melatonin for treatment of sleep disorders. Evid.Rep.Technol.Assess.(Summ.) 2004;(108):1-7.
- Cavallo, A., Ris, M. D., Succop, P., and Jaskiewicz, J. Melatonin treatment of pediatric residents for adaptation to night shift work. Ambul.Pediatr. 2005;5(3):172-177. PubMed
- Faber, M. S., Jetter, A., and Fuhr, U. Assessment of CYP1A2 activity in clinical practice: why, how, and when? Basic Clin Pharmacol Toxicol. 2005;97(3):125-134. PubMed
- Cagnacci, A., Cannoletta, M., Renzi, A., Baldassari, F., Arangino, S., and Volpe, A. Prolonged melatonin administration decreases nocturnal blood pressure in women. Am J Hypertens. 2005;18(12 Pt 1):1614-1618. PubMed
- Weekley, L. B. Melatonin-induced relaxation of rat aorta: interaction with adrenergic agonists. J Pineal Res 1991;11(1):28-34. PubMed
- Grossman, E., Laudon, M., Yalcin, R., Zengil, H., Peleg, E., Sharabi, Y., Kamari, Y., Shen-Orr, Z., and Zisapel, N. Melatonin reduces night blood pressure in patients with nocturnal hypertension. Am J Med 2006;119(10):898-902. PubMed
- van der Heijden, K. B., Smits, M. G., van Someren, E. J., Ridderinkhof, K. R., and Gunning, W. B. Effect of melatonin on sleep, behavior, and cognition in ADHD and chronic sleep-onset insomnia. J Am Acad.Child Adolesc.Psychiatry 2007;46(2):233-241. PubMed
- Klupinska, G., Poplawski, T., Drzewoski, J., Harasiuk, A., Reiter, R. J., Blasiak, J., and Chojnacki, J. Therapeutic effect of melatonin in patients with functional dyspepsia. J.Clin.Gastroenterol. 2007;41(3):270-274. PubMed
- Bjorvatn, B., Stangenes, K., Oyane, N., Forberg, K., Lowden, A., Holsten, F., and Akerstedt, T. Randomized placebo-controlled field study of the effects of bright light and melatonin in adaptation to night work. Scand.J Work Environ.Health 2007;33(3):204 PubMed
- Wirtz, P. H., Spillmann, M., Bartschi, C., Ehlert, U., and von Kanel, R. Oral melatonin reduces blood coagulation activity: a placebo-controlled study in healthy young men. J Pineal Res 2008;44(2):127-133. PubMed
- Bendz, L. M. and Scates, A. C. Melatonin treatment for insomnia in pediatric patients with attention-deficit/hyperactivity disorder. Ann.Pharmacother. 2010;44(1):185-191. PubMed
- Elkhayat, H. A., Hassanein, S. M., Tomoum, H. Y., Abd-Elhamid, I. A., Asaad, T., and Elwakkad, A. S. Melatonin and sleep-related problems in children with intractable epilepsy. Pediatr.Neurol. 2010;42(4):249-254. PubMed
- van Geijlswijk, I. M., van der Heijden, K. B., Egberts, A. C., Korzilius, H. P., and Smits, M. G. Dose finding of melatonin for chronic idiopathic childhood sleep onset insomnia: an RCT. Psychopharmacology (Berl) 2010;212(3):379-391. PubMed
- Wade AG, Ford I, Crawford G, et al. Nightly treatment of primary insomnia with prolonged release melatonin for 6 months: a randomized placebo controlled trial on age and endogenous melatonin as predictors of efficacy and safety. BMC Med 2010;8:51. PubMed
- Al-Aama, T., Brymer, C., Gutmanis, I., Woolmore-Goodwin, S. M., Esbaugh, J., and Dasgupta, M. Melatonin decreases delirium in elderly patients: a randomized, placebo-controlled trial. Int.J.Geriatr.Psychiatry 2011;26(7):687-694. PubMed
- Alstadhaug, K. B., Odeh, F., Salvesen, R., and Bekkelund, S. I. Prophylaxis of migraine with melatonin: a randomized controlled trial. Neurology 10-26-2010;75(17):1527-1532. PubMed
- Wade, A. G., Crawford, G., Ford, I., McConnachie, A., Nir, T., Laudon, M., and Zisapel, N. Prolonged release melatonin in the treatment of primary insomnia: evaluation of the age cut-off for short- and long-term response. Curr.Med.Res.Opin. 2011;27(1):87 PubMed
- van Geijlswijk, I. M., Korzilius, H. P., and Smits, M. G. The use of exogenous melatonin in delayed sleep phase disorder: a meta-analysis. Sleep 2010;33(12):1605-1614. PubMed
- Guenole, F., Godbout, R., Nicolas, A., Franco, P., Claustrat, B., and Baleyte, J. M. Melatonin for disordered sleep in individuals with autism spectrum disorders: systematic review and discussion. Sleep Med.Rev. 2011;15(6):379-387. PubMed
- Rossignol, D. A. and Frye, R. E. Melatonin in autism spectrum disorders: a systematic review and meta-analysis. Dev.Med.Child Neurol. 2011;53(9):783-792. PubMed
- Eryilmaz, O. G., Devran, A., Sarikaya, E., Aksakal, F. N., Mollamahmutoglu, L., and Cicek, N. Melatonin improves the oocyte and the embryo in IVF patients with sleep disturbances, but does not improve the sleeping problems. J.Assist.Reprod.Genet. 2011;28 PubMed
- Batioglu, A. S., Sahin, U., Gurlek, B., Ozturk, N., and Unsal, E. The efficacy of melatonin administration on oocyte quality. Gynecol.Endocrinol. 2012;28(2):91-93.
- Grossman, E., Laudon, M., and Zisapel, N. Effect of melatonin on nocturnal blood pressure: meta-analysis of randomized controlled trials. Vasc.Health Risk Manag. 2011;7:577-584. PubMed
- Nickelsen, T., Demisch, L., Demisch, K., Radermacher, B., and Schoffling, K. Influence of subchronic intake of melatonin at various times of the day on fatigue and hormonal levels: a placebo-controlled, double-blind trial. J Pineal Res 1989;6(4):325-334. PubMed
- Wright, J., Aldhous, M., Franey, C., English, J., and Arendt, J. The effects of exogenous melatonin on endocrine function in man. Clin Endocrinol (Oxf) 1986;24(4):375-382. PubMed
- Papavasiliou, P. S., Cotzias, G. C., Duby, S. E., Steck, A. J., Bell, M., and Lawrence, W. H. Melatonin and parkinsonism. JAMA 7-3-1972;221(1):88-89. DOI
- Middleton, B. A., Stone, B. M., and Arendt, J. Melatonin and fragmented sleep patterns. Lancet 8-24-1996;348(9026):551-552. PubMed
- Holliman, B. J. and Chyka, P. A. Problems in assessment of acute melatonin overdose. South.Med J 1997;90(4):451-453. PubMed
- Hong, Y. G. and Riegler, J. L. Is melatonin associated with the development of autoimmune hepatitis? J Clin Gastroenterol 1997;25(1):376-378. PubMed
- Cagnacci, A., Arangino, S., Angiolucci, M., Maschio, E., and Melis, G. B. Influences of melatonin administration on the circulation of women. Am J Physiol 1998;274(2 Pt 2):R335-R338. PubMed
- U.S.Food and Drug Administration. Special Nutritionals Adverse Events Monitoring System: registered case reports.
- Brueske V, Allen J, Kepic T, and et al. Melatonin inhibition of seizure activity in man [abstract]. Electroencephalog Clin Neurophysiol 1981;51:20P.
- Siddiqui MA, Nazmi AS, Karim S, and et al. Effect of melatonin and valproate in epilepsy and depression. Indian J Pharmacol 2001;33:378-381.
- Appleton RE, Jones AP, Gamble C, et al. The use of MElatonin in children with neurodevelopmental disorders and impaired sleep: a randomised, double-blind, placebo-controlled, parallel study (MENDS). Health Technol Assess. 2012;16(40):i-239. PubMed
- Bardazzi F, Placucci F, Neri I, D'Antuono A, Patrizi A. Fixed drug eruption due to melatonin. Acta Derm Venereol. 1998 Jan;78(1):69-70. PubMed
- Eckerberg B, Lowden A, Nagai R, Akerstedt T. Melatonin treatment effects on adolescent students' sleep timing and sleepiness in a placebo-controlled crossover study. Chronobiol Int. 2012;29(9):1239-48.
- Khezri MB, Merate H. The effects of melatonin on anxiety and pain scores of patients, intraocular pressure, and operating conditions during cataract surgery under topical anesthesia. Indian J Ophthalmol. 2013;61(7):319-24. PubMed
- Khezri MB, Oladi MR, Atlasbaf A. Effect of melatonin and gabapentin on anxiety and pain associated with retrobulbar eye block for cataract surgery: a randomized double-blind study. Indian J Pharmacol. 2013;45(6):581-6. PubMed
- Nishihara T, Hashimoto S, Ito K, et al. Oral melatonin supplementation improves oocyte and embryo quality in women undergoing in vitro fertilization-embryo transfer. Gynecol Endocrinol. 2014;30(5):359-62.
- De Bleecker JL, Lamont BH, Verstraete AG, Schelfhout VJ. Melatonin and painful gynecomastia. Neurology. 1999 Jul 22;53(2):435-6. PubMed
- Waldron DL, Bramble D, Gringras P. Melatonin: prescribing practices and adverse events. Arch Dis Child. 2005 Nov;90(11):1206-7. PubMed
- Chojnacki C, Walecka-Kapica E, Lokiec K, et al. Influence of melatonin on symptoms of irritable bowel syndrome in postmenopausal women. Endokrynol Pol. 2013;64(2):114-20.
- Kim MK, Park EA, Kim HJ, et al. Does supplementation of in-vitro culture medium with melatonin improve IVF outcome in PCOS? Reprod Biomed Online. 2013;26(1):22-9. PubMed
- Silman RE. Melatonin: a contraceptive for the nineties. Eur J Obstet Gynecol Reprod Biol. 1993;49(1-2):3-9. PubMed
- Briggs GG, Freeman RK, Forinash AB, Towers CV. Drugs in Pregnancy and Lactation. 11th ed. Philadelphia, PA: Wolters Kluwer, 2017.
- Onseng K, Johns NP, Khuayjarernpanishk T, et al. Beneficial Effects of Adjuvant Melatonin in Minimizing Oral Mucositis Complications in Head and Neck Cancer Patients Receiving Concurrent Chemoradiation. J Altern Complement Med 2017;23(12):957-63. PubMed
- Foster BC, Cvijovic K, Boon HS, et al. Melatonin Interaction Resulting in Severe Sedation. J Pharm Pharm Sci 2015;18(2):124-31. PubMed
- Gonçalves AL, Martini Ferreira A, Ribeiro RT, Zukerman E, Cipolla-Neto J, Peres MF. Randomised clinical trial comparing melatonin 3 mg, amitriptyline 25 mg and placebo for migraine prevention. J Neurol Neurosurg Psychiatry 2016;87(10):1127-32. PubMed
- Gringras P, Nir T, Breddy J, Frydman-Marom A, Findling RL. Efficacy and Safety of Pediatric Prolonged-Release Melatonin for Insomnia in Children With Autism Spectrum Disorder. J Am Acad Child Adolesc Psychiatry 2017;56(11):948-57.e4. PubMed
- Baandrup L, Lindschou J, Winkel P, Gluud C, Glenthoj BY. Prolonged-release melatonin versus placebo for benzodiazepine discontinuation in patients with schizophrenia or bipolar disorder: A randomised, placebo-controlled, blinded trial. World J Biol Psychi PubMed
- Lui MFG, Chow HKD, Wong WMK, Tsang WNW. Melatonin affects postural control in community-dwelling older adults while dual-tasking: a randomized observation study. J Aging Phys Act. 2018 May 29:1-24. PubMed
- Fallah R, Shoroki FF, Ferdosian F. Safety and efficacy of melatonin in pediatric migraine prophylaxis. Curr Drug Saf. 2015;10(2):132-5. PubMed
- Scheuer C, Pommergaard HC, Rosenberg J, Gogenur I. Effect of topical application of melatonin cream 12.5% on cognitive parameters: a randomized, placebo-controlled, double-blind crossover study in healthy volunteers. J Dermatolog Treat. 2016 Nov;27(6):488 PubMed
- Doosti-Irani A, Ostadmohammadi V, Mirhosseini N et al. The effects of melatonin supplementation on glycemic control: A systematic review and meta-analysis of randomized controlled trials. Horm Metab Res. 2018;50(11):783-790. PubMed
- Farrokhian A, Tohidi M, Ahanchi NS, et al. Effect of bedtime melatonin administration in patients with type 2 diabetes: A triple-blind, placebo-controlled, randomized trial. Iran J Pharm Res. 2019;18(Suppl1):258-268.
- Hayashi M, Mishima K, Fukumizu M, et al. Melatonin treatment and adequate sleep hygiene interventions in children with autism spectrum disorder: A randomized controlled trial. J Autism Dev Disord 2021. PubMed
- Esmaeili A, Nassiri Toosi M, Taher M, et al. A pilot randomized, clinical trial of the anti-pruritus effect of melatonin in patients with chronic liver disease. Iran J Pharm Res 2021;20(2):462-472.
- Yan W, Li C, Song X, Zhou W, Chen Z. Prophylactic melatonin for delirium in critically ill patients: A systematic review and meta-analysis with trial sequential analysis. Medicine (Baltimore) 2022;101(43):e31411. PubMed
- Ameri A, Frouz Asadi M, Ziaei A, et al. Efficacy and safety of oral melatonin in patients with severe COVID-19: a randomized controlled trial. Inflammopharmacology 2023;31(1):265-274. PubMed
- Ha M, Yoon D, Lee CY, et al. Investigating the safety profiles of exogenous melatonin and associated adverse events: A pharmacovigilance study using WHO-VigiBase. J Pineal Res 2024;76(2):e12949. PubMed
Theanine 6 references
- Yokogoshi H, Kobayashi M. Hypotensive effect of gamma-glutamylethylamide in spontaneously hypertensive rats. Life Sci 1998;62:1065-8.
- Haskell, C. F., Kennedy, D. O., Milne, A. L., Wesnes, K. A., and Scholey, A. B. The effects of L-theanine, caffeine and their combination on cognition and mood. Biol.Psychol. 2008;77(2):113-122. PubMed
- Yokogoshi, H., Kato, Y., Sagesaka, Y. M., Takihara-Matsuura, T., Kakuda, T., and Takeuchi, N. Reduction effect of theanine on blood pressure and brain 5-hydroxyindoles in spontaneously hypertensive rats. Biosci.Biotechnol.Biochem. 1995;59(4):615-618. PubMed
- Lyon MR, Kapoor MP, Juneja LR. The effects of L-theanine (Suntheanine®) on objective sleep quality in boys with attention deficit hyperactivity disorder (ADHD): a randomized, double-blind, placebo-controlled clinical trial. Altern Med Rev. 2011;16(4):348-
- Hidese S, Ota M, Wakabayashi C, et al. Effects of chronic l-theanine administration in patients with major depressive disorder: an open-label study. Acta Neuropsychiatr 2017;29(2):72-9.
- Tsuchiya T, Honda H, Oikawa M, et al. Oral administration of the amino acids cystine and theanine attenuates the adverse events of S-1 adjuvant chemotherapy in gastrointestinal cancer patients. Int J Clin Oncol 2016;21(6):1085-90. PubMed
5-htp 32 references
- Birdsall TC. 5-Hydroxytryptophan: A Clinically-Effective Serotonin Precursor. Altern Med Rev 1998;3:271-80.
- Michelson D, Page SW, Casey R, et al. An eosinophilia-myalgia syndrome related disorder associated with exposure to L-5-hydroxytryptophan. J Rheumatol 1994;21:2261-5.
- Cangiano C, Ceci F, Cancino A, et al. Eating behavior and adherence to dietary prescriptions in obese adult subjects treated with 5-hydroxytryptophan. Am J Clin Nutr 1992;56:863-7. PubMed
- U.S. Food and Drug Administration. Impurities confirmed in dietary supplement 5-hydroxy-L-tryptophan. FDA Talk Paper, August 31, 1998; T98-48.
- Sternberg EM, Van Woert MH, Young SN, et al. Development of a scleroderma-like illness during therapy with L-5-hydroxytryptophan and carbidopa. N Engl J Med 1980;303:782-7. PubMed
- Poldinger W, Calanchini B, Schwarz W. A functional-dimensional approach to depression: serotonin deficiency as a target syndrome in a comparison of 5-hydroxytryptophan and fluvoxamine. Psychopathology 1991;24:53-81.
- Ribeiro CA. L-5-Hydroxytryptophan in the prophylaxis of chronic tension-type headache: a double-blind, randomized, placebo-controlled study. Headache 2000;40:451-6.
- U. S. Food and Drug Administration, Center for Food Safety and Applied Nutrition, Office of Nutritional Products, Labeling, and Dietary Supplements. Information Paper on L-Tryptophan and 5-hydroxy-L-tryptophan, February 2001.
- Singhal AB, Caviness VS, Begleiter AF, et al. Cerebral vasoconstriction and stroke after use of serotonergic drugs. Neurology 2002;58:130-3. PubMed
- Johnson KL, Klarskov K, Benson LM, et al. Presence of peak X and related compounds: the reported contaminant in case related 5-hydroxy-L-tryptophan associated with eosinophilia-myalgia syndrome. J Rheumatol 1999;26:2714-7.
- Takahashi S, Kondo H, Kato N. Effect of l-5-hydroxytryptophan on brain monoamine metabolism and evaluation of its clinical effect in depressed patients. J Psychiatr Res 1975;12:177-87. PubMed
- Iovieno, N., Dalton, E. D., Fava, M., and Mischoulon, D. Second-tier natural antidepressants: review and critique. J Affect.Disord. 2011;130(3):343-357. PubMed
- den Boer JA, Westenberg HG. Behavioral, neuroendocrine, and biochemical effects of 5-hydroxytryptophan administration in panic disorder. Psychiatry Res 1990;31:267-78. PubMed
- Jangid P, Malik P, Singh P, Sharma M, Gulia AK. Comparative study of efficacy of l-5-hydroxytryptophan and fluoxetine in patients presenting with first depressive episode. Asian J Psychiatr 2013;6:29-34. PubMed
- Ceci F, Cangiano C, Cairella M, et al. The effects of oral 5-hydroxytryptophan administration on feeding behavior in obese adult female subjects. J Neural Transm 1989;76:109-17. PubMed
- Angst J, Woggon B, Schoepf J. The treatment of depression with L-5-hydroxytryptophan versus imipramine. Results of two open and one double-blind study. Arch Psychiatr Nervenkr 1977;224:175-86. DOI
- Titus F, Dávalos A, Alom J, Codina A. 5-Hydroxytryptophan versus methysergide in the prophylaxis of migraine. Randomized clinical trial. Eur Neurol 1986;25:327-9. PubMed
- De Benedittis G, Massei R. Serotonin precursors in chronic primary headache. A double-blind cross-over study with L-5-hydroxytryptophan vs. placebo. J Neurosurg Sci 1985;29:239-48.
- Van Woert, M. H., Rosenbaum, D., Howieson, J., and Bowers, M. B., Jr. Long-term therapy of myoclonus and other neurologic disorders with L-5- hydroxytryptophan and carbidopa. N Engl J Med 1-13-1977;296(2):70-75. PubMed
- Wyatt, R. J., Vaughan, T., Galanter, M., Kaplan, J., and Green, R. Behavioral changes of chronic schizophrenic patients given L-5- hydroxytryptophan. Science 9-22-1972;177(54):1124-1126. PubMed
- Chase, T. N., Ng, L. K., and Watanabe, A. M. Parkinson's disease. Modification by 5-hydroxytryptophan. Neurology 1972;22(5):479-484.
- van Hiele LJ. l-5-Hydroxytryptophan in depression: the first substitution therapy in psychiatry? The treatment of 99 out-patients with 'therapy-resistant' depressions. Neuropsychobiology 1980;6:230-40. PubMed
- Pranzatelli, M. R., Tate, E., Huang, Y., Haas, R. H., Bodensteiner, J., Ashwal, S., and Franz, D. Neuropharmacology of progressive myoclonus epilepsy: response to 5- hydroxy-L-tryptophan. Epilepsia 1995;36(8):783-791. PubMed
- Trouillas P, Serratrice G, Laplane D, et al. Levorotatory form of 5-hydroxytryptophan in Friedreich's ataxia. Results of a double-blind drug-placebo cooperative study. Arch Neurol 1995;52:456-60. PubMed
- Bastard, J., Truelle, J. L., and Emile, J. [Effectiveness of 5 hydroxy-tryptophan in Parkinson's disease]. Nouv Presse Med 9-11-1976;5(29):1836-1837.
- Auffret, M., Comte, H., and Bene, J. Eosinophilia-myalgia syndrome induced by L-5 hydroxytryptophane: about three cases. Fund Clin Pharmacol 2013;Suppl 1(120):poster P2-204.
- Wyatt, R. J., Vaughan, T., Kaplan, J., Galanter, M., and Green, R. 5-Hydroxytryptophan and chronic schizophrenia. In: Barchas J and Usdin E. Serotonin and Behavior. New York: Acedemic Press;1973.
- Das YT, Bagchi M, Bagchi D, Preuss HG. Safety of 5-hydroxy-L-tryptophan. Toxicol Lett 2004;150:111-22. PubMed
- Pardo JV. Mania following addition of hydroxytryptophan to monoamine oxidase inhibitor. Gen Hosp Psychiatry 2012;34(1):102.e13-4. PubMed
- Michelson D, Page SW, Casey R, et al. An eosinophilia-myaligia syndrome related disorder associated with exposure to l-5-hydroxytryptophan. J Rheumatol 1994;21(12):2261-5.
- Yousefzadeh F, Sahebolzamani E, Sadri A, et al. 5-Hydroxytryptophan as adjuvant therapy in treatment of moderate to severe obsessive-compulsive disorder: a double-blind randomized trial with placebo control. Int Clin Psychopharmacol. 2020;35(5):254-262. PubMed
- Maffei ME. 5-Hydroxytryptophan (5-HTP): Natural Occurrence, Analysis, Biosynthesis, Biotechnology, Physiology and Toxicology. Int J Mol Sci. 2020;22(1):181. PubMed
Magnesium 82 references
- Rodin SM, Johnson BF. Pharmacokinetic interactions with digoxin. Clin Pharmacokinet 1988;15:227-44.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Dahle LO, Berg G, Hammar M, et al. The effect of oral magnesium substitution on pregnancy-induced leg cramps. Am J Obstet Gynecol 1995;173:175-80. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Peikert A, Wilimzig C, Kohne-Volland R. Prophylaxis of migraine with oral magnesium: results from a prospective, multi-center, placebo-controlled and double-blind randomized study. Cephalalgia 1996;16:257-63. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Washington, DC: National Academy Press, 1999. Available at: http://books.nap.edu/books/0309063507/html/index.html.
- Birrer RB, Shallash AJ, Totten V. Hypermagnesemia-induced fatality following epsom salt gargles. J Emerg Med 2002;22:185-8. PubMed
- Ryan MP. Diuretics and potassium/magnesium depletion. Directions for treatment. Am J Med 1987;82:38-47.. PubMed
- Hollifield JW. Magnesium depletion, diuretics, and arrhythmias. Am J Med 1987;82:30-7.. PubMed
- Heidenreich O. Mode of action of conventional and potassium-sparing diuretics--aspects with relevance to Mg-sparing effects. Magnesium 1984;3:248-56..
- Pfaffenrath V, Wessely P, Meyer C, et al. Magnesium in the prophylaxis of migraine--a double-blind placebo-controlled study. Cephalalgia 1996;16:436-40.. PubMed
- Wang F, Van Den Eeden SK, Ackerson LM, et al. Oral magnesium oxide prophylaxis of frequent migrainous headache in children: a randomized, double-blind, placebo-controlled trial. Headache 2003;43:601-10.. PubMed
- Sompolinsky D, Samra Z. Influence of magnesium and manganese on some biological and physical properties of tetracycline. J Bacteriol 1972;110:468-76.. PubMed
- Jeyabalan A, Caritis SN. Pharmacologic inhibition of preterm labor. Clin Obstet Gynecol 2002;45:99-113. PubMed
- Mittendorf R, Dambrosia J, Pryde PG, et al. Association between the use of antenatal magnesium sulfate in preterm labor and adverse health outcomes in infants. Am J Obstet Gynecol 2002;186:1111-8.. PubMed
- Witlin AG, Sibai BM. Magnesium sulfate therapy in preeclampsia and eclampsia. Obstet Gynecol 1998;92:883-9.. DOI
- Crowther CA, Hiller JE, Doyle LW. Magnesium sulphate for preventing preterm birth in threatened preterm labour. Cochrane Database Syst Rev 2002;4:CD001060. . PubMed
- Davey MJ, Teubner D. A randomized controlled trial of magnesium sulfate, in addition to usual care, for rate control in atrial fibrillation. Ann Emerg Med 2005;45:347-53.. PubMed
- L'Hommedieu CS, Nicholas D, Armes DA, et al. Potentiation of magnesium sulfate--induced neuromuscular weakness by gentamicin, tobramycin, and amikacin. J Pediatr 1983;102:629-31..
- Dunn CJ, Goa KL. Risedronate: a review of its pharmacological properties and clinical use in resorptive bone disease. Drugs 2001;61:685-712..
- Kass L, Weekes J, Carpenter L. Effect of magnesium supplementation on blood pressure: a meta-analysis. Eur J Clin Nutr 2012;66:411-8. PubMed
- Koontz SL, Friedman SA, Schwartz ML. Symptomatic hypocalcemia after tocolytic therapy with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 2004;190(6):1773-6. PubMed
- Snyder SW, Cardwell MS. Neuromuscular blockade with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 1989;161(1):35-6. PubMed
- Waisman GD, Mayorga LM, Cámera MI, et al. Magnesium plus nifedipine: potentiation of hypotensive effect in preeclampsia? Am J Obstet Gynecol. 1988;159(2):308-9. PubMed
- Brown DD, Juhl RP. Decreased bioavailability of digoxin due to antacids and kaolin-pectin. N Engl J Med. 1976;295(19):1034-7. PubMed
- Allen MD, Greenblatt DJ, Harmatz JS, et al. Effect of magnesium--aluminum hydroxide and kaolin--pectin on absorption of digoxin from tablets and capsules. J Clin Pharmacol. 1981;21(1):26-30. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an in vitro study. Thromb Haemost. 1996;76(1):88-93. DOI
- Ravn HB, Kristensen SD, Vissinger H, et al. Magnesium inhibits human platelets. Blood Coagul Fibrinolysis. 1996;7(2):241-4. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an infusion study in healthy volunteers. Thromb Haemost. 1996;75(6):939-44. DOI
- Neuvonen PJ, Kivistö KT. The effects of magnesium hydroxide on the absorption and efficacy of two glibenclamide preparations. Br J Clin Pharmacol. 1991;32(2):215-20. PubMed
- Kivistö KT, Neuvonen PJ. Enhancement of absorption and effect of glipizide by magnesium hydroxide. Clin Pharmacol Ther. 1991;49(1):39-43. PubMed
- Neuvonen PJ, Kivistö KT. Enhancement of drug absorption by antacids. An unrecognised drug interaction. Clin Pharmacokinet. 1994;27(2):120-8. PubMed
- Shechter, M., Merz, C. N., Paul-Labrador, M., Meisel, S. R., Rude, R. K., Molloy, M. D., Dwyer, J. H., Shah, P. K., and Kaul, S. Beneficial antithrombotic effects of the association of pharmacological oral magnesium therapy with aspirin in coronary heart
- Ganzevoort, J. W., Hoogerwaard, E. M., and van der Post, J. A. [Hypocalcemic delirium due to magnesium sulphate therapy in a pregnant woman with pre-eclampsia]. Ned.Tijdschr.Geneeskd. 8-3-2002;146(31):1453-1456.
- Horner, S. M. Efficacy of intravenous magnesium in acute myocardial infarction in reducing arrhythmias and mortality. Meta-analysis of magnesium in acute myocardial infarction. Circulation 1992;86(3):774-779. PubMed
- Azria, E., Tsatsaris, V., Goffinet, F., Kayem, G., Mignon, A., and Cabrol, D. [Magnesium sulfate in obstetrics: current data]. J Gynecol.Obstet.Biol.Reprod.(Paris) 2004;33(6 Pt 1):510-517.
- Magee, L. A., Miremadi, S., Li, J., Cheng, C., Ensom, M. H., Carleton, B., Cote, A. M., and von Dadelszen, P. Therapy with both magnesium sulfate and nifedipine does not increase the risk of serious magnesium-related maternal side effects in women with p
- Henyan, N. N., Gillespie, E. L., White, C. M., Kluger, J., and Coleman, C. I. Impact of intravenous magnesium on post-cardiothoracic surgery atrial fibrillation and length of hospital stay: a meta-analysis. Ann.Thorac.Surg. 2005;80(6):2402-2406. PubMed
- Li, J., Zhang, Q., Zhang, M., and Egger, M. Intravenous magnesium for acute myocardial infarction. Cochrane.Database.Syst.Rev. 2007;(2):CD002755. PubMed
- Doyle, L. W., Crowther, C. A., Middleton, P., Marret, S., and Rouse, D. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane.Database.Syst.Rev. 2009;(1):CD004661. PubMed
- Han, S., Crowther, C. A., and Moore, V. Magnesium maintenance therapy for preventing preterm birth after threatened preterm labour. Cochrane.Database.Syst.Rev. 2010;(7):CD000940. PubMed
- Duley, L., Gulmezoglu, A. M., Henderson-Smart, D. J., and Chou, D. Magnesium sulphate and other anticonvulsants for women with pre-eclampsia. Cochrane.Database.Syst.Rev. 2010;(11):CD000025. PubMed
- Conde-Agudelo, A., Romero, R., and Kusanovic, J. P. Nifedipine in the management of preterm labor: a systematic review and metaanalysis. Am J Obstet.Gynecol. 2011;204(2):134-20. PubMed
- Wong, G. K., Boet, R., Poon, W. S., Chan, M. T., Gin, T., Ng, S. C., and Zee, B. C. Intravenous magnesium sulphate for aneurysmal subarachnoid hemorrhage: an updated systemic review and meta-analysis. Crit Care 2011;15(1):R52. PubMed
- Magee, L., Sawchuck, D., Synnes, A., and von, Dadelszen P. SOGC Clinical Practice Guideline. Magnesium sulphate for fetal neuroprotection. J Obstet.Gynaecol.Can. 2011;33(5):516-529.
- Doyle, L. W. Antenatal magnesium sulfate and neuroprotection. Curr Opin Pediatr 2012;24(2):154-159. PubMed
- McDonald, S. D., Lutsiv, O., Dzaja, N., and Duley, L. A systematic review of maternal and infant outcomes following magnesium sulfate for pre-eclampsia/eclampsia in real-world use. Int J Gynaecol.Obstet. 2012;118(2):90-96. PubMed
- Gordon, M., Naidoo, K., Akobeng, A. K., and Thomas, A. G. Osmotic and stimulant laxatives for the management of childhood constipation. Cochrane.Database.Syst.Rev. 2012;7:CD009118. PubMed
- Dodd, J. M., Crowther, C. A., and Middleton, P. Oral betamimetics for maintenance therapy after threatened preterm labour. Cochrane.Database.Syst.Rev. 2012;12:CD003927. PubMed
- Wu, X., Wang, C., Zhu, J., Zhang, C., Zhang, Y., and Gao, Y. Meta-analysis of randomized controlled trials on magnesium in addition to beta-blocker for prevention of postoperative atrial arrhythmias after coronary artery bypass grafting. BMC.Cardiovasc.D PubMed
- Thorp, J. M., Jr., Katz, V. L., Campbell, D., and Cefalo, R. C. Hypersensitivity to magnesium sulfate. Am.J.Obstet.Gynecol. 1989;161(4):889-890. PubMed
- Duley L and Gulmezoglu AM. Magnesium sulphate versus lytic cocktail for eclampsia. Cochrane Database of Systematic Reviews 2000;(3) PubMed
- Gibbins KJ, Browning KR, Lopes VV, Anderson BL, Rouse DJ. Evaluation of the clinical use of magnesium sulfate for cerebral palsy prevention. Obstet Gynecol 2013;121(2 Pt 1):235-40. PubMed
- Ji D. Oral magnesium sulfate causes perforation during bowel preparation for fiberoptic colonoscopy in patients with colorectal cancer. J Emerg Med 2012;43(4):716-7. PubMed
- Yagi T, Naito T, Mino Y, Umemura K, Kawakami J. Impact of concomitant antacid administration on gabapentin plasma exposure and oral bioavailability in healthy adult subjects. Drug Metab Pharmacokinet 2012;27(2):248-54. PubMed
- Yamasaki M, Funakoshi S, Matsuda S, Imazu T, Takeda Y, Murakami T, Maeda Y. Interaction of magnesium oxide with gastric acid secretion inhibitors in clinical pharmacotherapy. Eur J Clin Pharmacol 2014;70(8):921-4. PubMed
- Choi ES, Jeong WJ, Ahn SH, Oh AY, Jeon YT, Do SH. Magnesium sulfate accelerates the onset of low-dose rocuronium in patients undergoing laryngeal microsurgery. J Clin Anesth. 2017 Feb;36:102-106. PubMed
- Ikee R, Toyoyama T, Endo T, Tsunoda M, Hashimoto N. Impact of sevelamer hydrochloride on serum magnesium concentrations in hemodialysis patients. Magnes Res. 2016 Apr 1;29(4):184-90. PubMed
- Miller ES, Sakowicz A, Leger E. Lange E, Yee LM. The association between receipt of intrapartum magnesium and postpartum hemorrhage. Am J Obstet Gynecol 2018;218(1 Suppl):S165.
- Rodríguez-Rubio L, Solis Garcia Del Pozo J, Nava E, Jordán J. Interaction between magnesium sulfate and neuromuscular blockers during the perioperative period. A systematic review and meta-analysis. J Clin Anesth. 2016;34:524-34. PubMed
- Brown RS. Magnesium Sulfate: Another Cause of a Solute Diuresis. Am J Kidney Dis. 2017;69(4):550-551. PubMed
- Park H, Qin R, Smith TJ, et al. North Central Cancer Treatment Group N10C2 (Alliance): a double-blind placebo-controlled study of magnesium supplements to reduce menopausal hot flashes. Menopause. 2015;22(6):627-32. PubMed
- Sakanoue M, Sanada J, Kanekura T. Skin eruption elicited by magnesium oxide (Maglax). J Dermatol. 2016;43(2):221-2.
- Iwamuro M, Saito S, Yoshioka M, et al. A Magnesium Oxide Bezoar. Intern Med. 2018;57(21):3087-3091. PubMed
- Vilchez G, Dai J, Kumar K, Mundy D, Kontopoulos E, Sokol RJ. Racial/ethnic disparities in magnesium sulfate neuroprotection: a subgroup analysis of a multicenter randomized controlled trial. J Matern Fetal Neonatal Med. 2018;31(17):2304-2311. PubMed
- Drug Safety Communication: FDA Recommends Against Prolonged Use of Magnesium Sulfate to Stop Pre-term Labor Due to Bone Changes in Exposed Babies. U.S. Food and Drug Administration (FDA), May 30, 2013. https://www.fda.gov/downloads/Drugs/DrugSafety/UCM353
- Committee Opinion: Magnesium Sulfate Use in Obstetrics. The American College of Obstetricians and Gynecologists Committee on Obstetric Practice Society for Maternal-Fetal Medicine, Number 652, January 2016. https://www.acog.org/Clinical-Guidance-and-Publi
- Kashihara Y, Terao Y, Yoda K, et al. Effects of magnesium oxide on pharmacokinetics of L-dopa/carbidopa and assessment of pharmacodynamic changes by a model-based simulation. Eur J Clin Pharmacol. 2019;75(3):351-361. PubMed
- Shepherd E, Salam RA, Manhas D, et al. Antenatal magnesium sulphate and adverse neonatal outcomes: A systematic review and meta-analysis. PLoS Med. 2019;16(12):e1002988. PubMed
- Hong JY, Hong JY, Choi YS, et al. Antenatal magnesium sulfate treatment and risk of necrotizing enterocolitis in preterm infants born at less than 32 weeks of gestation. Sci Rep. 2020;10(1):12826. PubMed
- Schuh S, Sweeney J, Rumantir M, et al. Effect of nebulized magnesium vs placebo added to albuterol on hospitalization among children with refractory acute asthma treated in the emergency department: a randomized clinical trial. JAMA. 2020;324(20):2038-20 PubMed
- Almeida CED, Carvalho LR, Andrade CVC, Nascimento PD Jr, Barros GAM, Modolo NSP. Effects of magnesium sulphate on the onset time of rocuronium at different doses: a randomized clinical trial. Braz J Anesthesiol. 2021;71(5):482-8. PubMed
- Gochi Valdovinos A, Arriaga-Redondo M, Dejuan Bitriá E, Pérez Rodríguez I, Márquez Isidro E, Blanco Bravo D. Prenatal therapy with magnesium sulphate and intestinal obstruction due to meconium in preterm newborns. An Pediatr (Engl Ed). 2022 Feb;96(2):138- PubMed
- Iio K, Kondo E, Shibata E, et al. Long-term tocolysis with magnesium sulfate as a risk factor for low bone mass: a case series. J Med Cases. 2022 Feb;13(2):47-50. PubMed
- Eiraku K, Uozumi Y, Hieda M, Maruyama T, Nomura H. A senile case of heart failure associated with hypermagnesemia induced by magnesium-containing laxative agent. Geriatr Gerontol Int. 2022;22(10):897-899.
- Enayati A, Gin JH, Sajeev JK, et al. Efficacy of intravenous magnesium for the management of non-post operative atrial fibrillation with rapid ventricular response: A systematic review and meta-analysis. J Cardiovasc Electrophysiol 2023;34(5):1286-1295. PubMed
- Su YH, Luo DC, Pang Y. Effects of intraoperative Magnesium sulfate infusion on emergency agitation during general anesthesia in patients undergoing radical mastectomy: a randomized controlled study. BMC Anesthesiol 2023;23(1):326. PubMed
- Han J, Park HY, Shin HJ, Chung SH, Do SH. Effects of magnesium sulphate on neostigmine-induced recovery from moderate neuromuscular blockade with rocuronium: a randomized controlled trial. Magnes Res 2023;36(2):31-39. PubMed
- Lee AT, Cordova JC, Jamplis RP, Pomicter GR. Posterior Reversible Encephalopathy Syndrome and Eclampsia in the Setting of Magnesium Toxicity: A Case Report. A A Pract 2023;17(11):e01726. PubMed
- Darmawan D, Rengganis I, Rumende CM, et al. Effectiveness and Safety of Nebulized Magnesium as Last Line Treatment in Adults with Acute Asthma Attack: A Systematic Review and Meta-Analysis. Acta Med Indones 2024;56(1):3-12.
- Shepherd ES, Goldsmith S, Doyle LW, et al. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane Database Syst Rev 2024;5(5):CD004661. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Cowhage 12 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Anon. Epidemiological notes and reports: Mucuna pruriens-associated pruritus--New Jersey. MMWR Morb Mortal Wkly Rep 1985;34:732-3.
- HP-200 in Parkinson's Disease study group. An alternative medicine treatment for Parkinson's disease: Results of a multicenter clinical trial. J Alt Comp Med 1995;1:249-55. DOI
- Infante ME, Perez AM, Simao MR, et al. Outbreak of acute toxic psychosis attributed to Mucuna pruriens. Lancet 1990;336:1129. PubMed
- Vaidya AB, Rajagopalan TG, Mankodi NA, et al. Treatment of Parkinson's disease with the cowhage plant-Mucuna pruriens Bak. Neurol India 1978;26:171-6.
- Vadivel V, Janardhanan K. Nutritional and anti-nutritional composition of velvet bean: an under-utilized food legume in south India. Int J Food Sci Nutr 2000;51:279-87. PubMed
- Akhtar MS, Qureshi AQ, Iqbal J. Antidiabetic evaluation of Mucuna pruriens, Linn seeds. J Pak Med Assoc 1990;40:147-50.
- Prakash, D., Niranjan, A., and Tewari, S. K. Some nutritional properties of the seeds of three Mucuna species. Int.J.Food Sci.Nutr. 2001;52(1):79-82.
- Vadivel, V. and Janardhanan, K. Nutritional and antinutritional characteristics of seven South Indian wild legumes. Plant Foods Hum.Nutr 2005;60(2):69-75. PubMed
- Creapure (Creatine Monohydrate). Toxicological Datasheet. Degussa BioActives. Available at: https://www.fda.gov/ohrms/DOCKETS/.../95s-0316-rpt0154-54-Ref-50-vol112.pdf.
- Pulikkalpura H, Kurup R, Mathew PJ, Baby S. Levodopa in Mucuna pruriens and its degradation. Sci Rep 2015;5:11078. PubMed
Phellodendron 22 references
- Chan E. Displacement of bilirubin from albumin by berberine. Biol Neonate 1993;63:201-8. PubMed
- Janbaz KH, Gilani AH. Studies on preventive and curative effects of berberine on chemical-induced hepatotoxicity in rodents. Fitoterapia 2000;71:25-33.. PubMed
- Wu X, Li Q, Xin H, Yu A, Zhong M. Effects of berberine on the blood concentration of cyclosporin A in renal transplanted recipients: clinical and pharmacokinetic study. Eur J Clin Pharmacol 2005;61:567-72. PubMed
- Garrison R, Chambliss WG. Effect of a proprietary Magnolia and Phellodendron extract on weight management: a pilot, double-blind, placebo-controlled clinical trial. Altern Ther Health Med 2006;12:50-4.
- Zhang Y, Li X, Zou D, et al. Treatment of type 2 diabetes and dyslipidemia with the natural plant alkaloid berberine. J Clin Endocrinol Metab 2008;93:2559-65. PubMed
- Budzinski JW, Foster BC, Vandenhoek S, Arnason JT. An in vitro evaluation of human cytochrome P450 3A4 inhibition by selected commercial herbal extracts and tinctures. Phytomedicine 2000;7:273-82. PubMed
- Chatterjee P, Franklin MR. Human cytochrome p450 inhibition and metabolic-intermediate complex formation by goldenseal extract and its methylenedioxyphenyl components. Drug Metab Dispos 2003;31:1391-7. PubMed
- Shanbhag, S. M., Kulkarni, H. J., and Gaitonde, B. B. Pharmacological actions of berberine on the central nervous system. Jpn.J Pharmacol 1970;20(4):482-487. PubMed
- Wu, J. F. and Liu, T. P. [Effects of berberine on platelet aggregation and plasma levels of TXB2 and 6-keto-PGF1 alpha in rats with reversible middle cerebral artery occlusion]. Yao Xue.Xue.Bao. 1995;30(2):98-102.
- Peng, W. H., Hsieh, M. T., and Wu, C. R. Effect of long-term administration of berberine on scopolamine-induced amnesia in rats. Jpn J Pharmacol 1997;74(3):261-266. DOI
- Sabir M and Bhide NK. Study of some pharmacological actions of berberine. Ind J Physiol & Pharmac 1971;15(3):111-132.
- Tripathi YB and Shukla SD. Berberis artistata inhibits PAF induced aggregation of rabbit platelets. Phytotherapy Research 1996;10:628-630.
- Yin, J., Xing, H., and Ye, J. Efficacy of berberine in patients with type 2 diabetes mellitus. Metabolism 2008;57(5):712-717. PubMed
- Zhang, H., Wei, J., Xue, R., Wu, J. D., Zhao, W., Wang, Z. Z., Wang, S. K., Zhou, Z. X., Song, D. Q., Wang, Y. M., Pan, H. N., Kong, W. J., and Jiang, J. D. Berberine lowers blood glucose in type 2 diabetes mellitus patients through increasing insulin re
- Guo, Y., Chen, Y., Tan, Z. R., Klaassen, C. D., and Zhou, H. H. Repeated administration of berberine inhibits cytochromes P450 in humans. Eur J Clin Pharmacol 2012;68(2):213-217. PubMed
- Wei, W., Zhao, H., Wang, A., Sui, M., Liang, K., Deng, H., Ma, Y., Zhang, Y., Zhang, H., and Guan, Y. A clinical study on the short-term effect of berberine in comparison to metformin on the metabolic characteristics of women with polycystic ovary syndro
- Hermann, R. and von, Richter O. Clinical evidence of herbal drugs as perpetrators of pharmacokinetic drug interactions. Planta Med 2012;78(13):1458-1477. PubMed
- Chun YT, Yip TT, Lau KL, and et al. A biochemical study on the hypotensive effect of berberine in rats. Gen Pharmac 1979;10:177-182. PubMed
- Hou Q, Han W, Fu X. Pharmacokinetic interaction between tacrolimus and berberine in a child with idiopathic nephrotic syndrome. Eur J Clin Pharmacol 2013;69(10):1861-2. PubMed
- Lan J, Zhao Y, Dong F, et al. Meta-analysis of the effect and safety of berberine in the treatment of type 2 diabetes mellitus, hyperlipemia and hypertension. J Ethnopharmacol. 2015;161:69-81. PubMed
- Kalman DS, Feldman S, Feldman R, et al. Effect of a proprietary magnolia and phellodendron extract on stress levels in healthy women: a pilot, double-blind, placebo-controlled clinical trial. Nutr J 2008;7:11.
- Lyu Y, Zhang Y, Yang M, et al. Pharmacokinetic interactions between metformin and berberine in rats: Role of oral administration sequences and microbiota. Life Sci. 2019;235:116818. PubMed
Gamma-aminobutyric Acid (gaba) 12 references
- Cavagnini F, Invitti C, Pinto M, et al. Effect of acute and repeated administration of gamma aminobutyric acid (GABA) on growth hormone and prolactin secretion in man. Acta Endocrinol (Copenh) 1980;93:149-54.
- Nurnberger JI Jr, Berrettini WH, Simmons-Alling S, et al. Intravenous GABA administration is anxiogenic in man. Psychiatry Res 1986;19:113-7. PubMed
- Gershman RN, Vasilenko MA, Iliushina GG, et al. [Gammalon in the rehabilitation in infantile cerebral palsy]. Pediatr.Akus.Ginekol. 1977;(6):26-7.
- Loeb C, Benassi E, Bo, GP, et al. Preliminary evaluation of the effect of GABA and phosphatidylserine in epileptic patients. Epilepsy Res. 1987;1:209-12 . PubMed
- Inoue K, Shirai T, Ochiai H, et al. Blood-pressure-lowering effect of a novel fermented milk containing gamma-aminobutyric acid (GABA) in mild hypertensives. Eur J Clin Nutr 2003;57:490-95.
- ELLIOTT, K. A. and JASPER, H. H. Gammaaminobutyric acid. Physiol Rev. 1959;39(2):383-406.
- Winsky-Sommerer, R. Role of GABAA receptors in the physiology and pharmacology of sleep. Eur.J.Neurosci. 2009;29(9):1779-1794.
- Meldrum, B. S. GABAergic mechanisms in the pathogenesis and treatment of epilepsy. Br.J.Clin.Pharmacol. 1989;27 Suppl 1:3S-11S. PubMed
- Loeb, C., Marinari, U. M., Benassi, E., Besio, G., Cottalasso, D., Cupello, A., Maffini, M., Mainardi, P., Pronzato, M. A., and Scotto, P. A. Phosphatidylserine increases in vivo the synaptosomal uptake of exogenous GABA in rats. Exp.Neurol. 1988;99(2):4 PubMed
- Melis, G. B., Paoletti, A. M., Mais, V., and Fioretti, P. Interference of dopamine infusion on gamma-amino butyric acid (GABA)-stimulated prolactin increase. J.Endocrinol.Invest 1980;3(4):445-448.
- Boonstra E, de Kleijn R, Colzato LS, Alkemade A, Forstmann BU, Nieuwenhuis S. Neurotransmitters as food supplements: the effects of GABA on brain and behavior. Front Psychol. 2015 Oct 6;6:1520. doi: 10.3389/fpsyg.2015.01520. eCollection 2015. PubMed
- de Bie TH, Witkamp RF, Balvers MG, Jongsma MA. Effects of ?-aminobutyric acid supplementation on glucose control in adults with prediabetes: A double-blind, randomized, placebo-controlled trial. Am J Clin Nutr 2023;118(3):708-719. PubMed
See these in context on the Gamma-aminobutyric Acid (gaba) monograph →
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC