
Boost with Testofen Ingredients & Drug Interactions
by Trojan Man
What is this page for?
First and foremost: checking Boost with Testofen against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Boost with Testofen is a dietary supplement by Trojan Man with 10 active ingredients. Its ingredients are commonly taken for bone health and osteoporosis, correcting vitamin d deficiency, immune system support.Based on those ingredients, 1,411 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Bioperine, Horny Goat Weed Leaf, Stem Extract, Niacin. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Boost with Testofen by Trojan Man
Ask about any prescription or over-the-counter medication and we check it for interactions with Boost with Testofen by Trojan Man — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Boost with Testofen by Trojan Man
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Partial disclosure
Boost with Testofen contains 10 active ingredients. L-arginine and L-citrulline are amino acids that your body converts to nitric oxide, which relaxes blood vessels and improves blood flow.
Vitamin D3 supports bone health and calcium absorption. Zinc helps immune function and protein synthesis.
Niacin (vitamin B3) supports energy metabolism. Vitamin B12 is essential for nerve function and red blood cells.
Bioperine is a black pepper extract added to enhance absorption of the other ingredients. Magnesium plays a role in muscle function and energy production.
Testofen is a fenugreek seed extract marketed for sexual function. Horny goat weed leaf extract is included for similar purposes.
The product also contains inactive ingredients—cellulose, microcrystalline cellulose, magnesium stearate, silicon dioxide, and water—which are fillers and binders that hold the capsule together.
Does it work?
Moderate evidence
The evidence supporting these ingredients varies widely. L-citrulline shows possibly effective evidence for athletic performance, though evidence for cardiovascular disease and diabetes is insufficient to rate.
Vitamin D3 is effective for treating rickets, osteomalacia, renal bone disease, and hypoparathyroidism, but evidence for other uses isn't established in our data. Zinc is effective for zinc deficiency and likely effective for Wilson disease; it's possibly effective for acne and age-related macular degeneration.
Niacin is likely effective for pellagra and possibly effective for metabolic syndrome. Vitamin B12 is effective for vitamin B12 deficiency and imerslund-Grasbeck disease.
L-citrulline for sarcopenia rates as possibly ineffective. For L-arginine, Testofen (fenugreek), horny goat weed, bioperine, and magnesium in the context of sexual function or testosterone boost, the data we hold either shows insufficient evidence or doesn't rate those specific uses—so we cannot tell you this product works for those purposes based on the information available to us.
How safe is it?
Well-documented data
Most ingredients in this product are generally well tolerated at recommended doses, though safety profiles vary. L-arginine can lower blood pressure and requires medical supervision; adverse effects include abdominal pain, bloating, nausea, diarrhea, and headache.
L-citrulline is generally well tolerated but may cause gastrointestinal discomfort or heartburn. Vitamin D3 is safe at recommended doses but can cause toxicity at very high doses with symptoms of high blood calcium; it's likely safe in pregnancy and lactation.
Zinc is well tolerated below 40 mg daily but high doses can cause copper deficiency; common side effects are abdominal cramps, diarrhea, metallic taste, nausea, and vomiting. Niacin commonly causes flushing (up to 70% of users), gastrointestinal complaints, and elevated liver enzymes, especially at high doses.
Vitamin B12 is very safe and considered safe in pregnancy and lactation. Magnesium can cause diarrhea, nausea, vomiting, and gastrointestinal irritation, especially at higher doses.
Bioperine (black pepper) is generally safe as a food spice but concentrated supplements warrant caution. Testofen (fenugreek) may cause abdominal pain, bloating, diarrhea, and nausea, and the data advises against use during pregnancy.
Horny goat weed has limited human safety data; short-term use may be tolerated, but adverse effects include dizziness, dry mouth, nosebleed, and vomiting, and the data advises against use in pregnancy and lactation.
Meds to double-check
Major interaction found
Before you take Boost with Testofen, check with your pharmacist if you're on any of these: Parkinson's medications (especially levodopa/carbidopa—this is the most serious interaction), blood pressure medications, blood thinners or antiplatelet drugs, diabetes medications, antibiotics (quinolones, tetracyclines, or cephalosporins), heart rate or rhythm drugs, potassium-sparing diuretics, or antiretroviral drugs for HIV. L-arginine and L-citrulline can dangerously lower blood pressure when combined with antihypertensives, ACE inhibitors, or ARBs.
Magnesium significantly reduces levodopa absorption. Zinc and magnesium interfere with several antibiotic and HIV drug classes.
Bioperine can raise blood levels of phenytoin and several other medications. Your exact medications matter—use the checker below.
The bottom line
Scorecard at a glancePartially disclosed formula with some supporting evidence for its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
This product is marketed for sexual function and testosterone support, but evidence for those specific uses isn't established in our data. Anyone taking blood pressure medications, blood thinners, diabetes drugs, antibiotics (especially quinolones or tetracyclines), heart medications (like digoxin or calcium channel blockers), or Parkinson's medications should talk with their pharmacist or doctor before starting this product, because several ingredients carry documented interactions.
People with low blood pressure, kidney or liver problems, or those who are pregnant or breastfeeding should also check with their doctor first.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 10 of 10 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Sep 25, 2024.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Boost with Testofen, straight from the product label.
| Brand | Trojan Man |
|---|---|
| Net contents | 60 Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Sep 25, 2024 |
| DSLD ID | 317559 |
| Product type | Botanical With Nutrients |
| Supplement form | Capsule |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult Male (18-50 Years) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
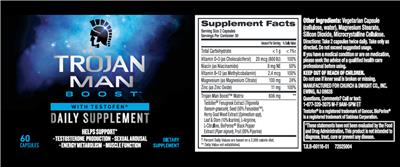
Supplement Facts
The label details for Boost with Testofen by Trojan Man, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Total Carbohydrates | 1 Gram(s) | 1% |
| L-Arginine | 0 NP | -- |
| L-Citrulline | 0 NP | -- |
| Vitamin D3 | 20 mcg | 100% |
| Zinc | 11 mg | 100% |
| Niacin | 8 mg NE | 50% |
| Vitamin B12 | 2.4 mcg | 100% |
| Bioperine | 0 NP | -- |
| Magnesium | 100 mg | 24% |
| Testofen | 0 NP | -- |
| Trojan Man Boost Complex | 606 mg | -- |
| Horny Goat Weed Leaf, Stem Extract | 0 NP | -- |
Other ingredients: Cellulose, Water, Magnesium Stearate, Silicon Dioxide, Microcrystalline Cellulose
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
FDA Statement of Identity
Daily Supplement
Dietary Supplement
Formulation
Helps support Testosterone production Sexual arousal Energy metabolism Muscle function
Suggested/Recommended/Usage/Directions
Directions: Take 2 capsules twice daily. Take only as directed. Do not exceed suggested usage.
Precautions
If you have a medical condition or are on medication, please seek the advice of a qualified health care professional before using.
Keep out of reach of children.
Do not exceed suggested usage. Do not use if inner seal is broken or missing.
General Statements
Questions, Comments? Call or text: 1-877-320-3075 M-F 9AM-5PM ET
Brand IP Statement(s)
Testofen is a registered trademark of Gencor. BioPerine is a registered trademark of Sabinsa Corporation.
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure or prevent any disease.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Boost with Testofen by Trojan Man label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Boost with Testofen by Trojan Man
These are the 10 active ingredients this product is made of. Select any to open its full monograph.
Serving size2 Capsule(s) Dosage formCapsule Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Vitamin D3
Interacts with715 drugs
Vitamin D is a fat-soluble vitamin that helps your body absorb calcium and is important for healthy bones, muscles, and immune function. Many people,...
Vitamin D3 monograph & interactionsZinc
Interacts with67 drugs
Zinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but suppleme...
Zinc monograph & interactionsNiacin
Interacts with727 drugs
Niacin (vitamin B3) is an essential nutrient your body needs for energy and metabolism, and deficiency is uncommon in most developed countries. Prescr...
Niacin monograph & interactionsVitamin B12
Interacts with20 drugs
Vitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very h...
Vitamin B12 monograph & interactionsMagnesium
Interacts with295 drugs
Magnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preven...
Magnesium monograph & interactionsTrojan Man Boost Complex
Other (inactive) ingredients: Cellulose, Water, Magnesium Stearate, Silicon Dioxide, Microcrystalline Cellulose. These complete the product’s ingredient list but are not active constituents.
Boost with Testofen by Trojan Man Drug Interactions
HelloPharmacist Interaction Report
Boost with Testofen by Trojan Man contains 10 active and ingredient components, several of which have documented interactions with medications.
The most serious interaction we've identified is a Major interaction: magnesium can reduce levodopa/carbidopa levels by up to 35% for levodopa and 81% for carbidopa, potentially lessening the medication's effectiveness for Parkinson's disease.
Read the full breakdown — every affected drug type, severity by severity
Multiple ingredients interact with antihypertensive drugs (blood pressure medications) at Moderate severity—including L-arginine, L-citrulline, niacin, and horny goat weed—because they can lower blood pressure further and increase the risk of excessively low pressure. L-arginine also interacts with ACE inhibitors and ARBs (common blood pressure and heart drugs), raising risks of both low blood pressure and high potassium levels.
Zinc can reduce absorption of several antibiotic types (quinolones, cephalexin, tetracyclines) and antiretroviral drugs (ritonavir, integrase inhibitors, bictegravir-containing combinations), so timing of doses matters. Magnesium similarly reduces quinolone and bisphosphonate absorption and can potentiate skeletal muscle relaxants.
L-arginine, L-citrulline, niacin, and fenugreek (Testofen) all carry Moderate interactions with blood thinners and antiplatelet drugs (warfarin, clopidogrel, aspirin-type agents) due to additive effects on bleeding. L-arginine and niacin both interact with diabetes medications—L-arginine can lower blood sugar, while niacin can raise it and reduce drug effectiveness.
Bioperine (black pepper) increases blood levels of several medications including phenytoin, propranolol, theophylline, and others, potentially raising side effects. Horny goat weed may inhibit liver enzymes (CYP1A2, CYP2B6, CYP3A4), theoretically increasing effects of drugs metabolized by those pathways.
Altogether, these interactions span 1,389 individual medications. We could not check Trojan Man Boost Complex (a proprietary blend) for interactions.
To know whether any of your specific prescriptions or over-the-counter drugs are affected, use the medication checker below with your exact drug names and doses.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Boost with Testofen?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Boost with Testofen interact with 1,411 drugs. Click any drug to see the details.
10 of the 10 ingredients in Boost with Testofen interact with drugs. Each result below shows which ingredient is responsible. Bioperine Horny Goat Weed Leaf, Stem Extract Niacin Vitamin D3 L-Arginine Testofen Magnesium L-Citrulline Zinc Vitamin B12
Benserazide, LevodopaMadopar, Prolopa
How Benserazide, Levodopa interacts with Boost with Testofen — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Benserazide, Levodopa interactionCarbidopaLodosyn
How Carbidopa interacts with Boost with Testofen — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa interactionCarbidopa, LevodopaDhivy, Rytary, Sinemet, Sinemet CR
How Carbidopa, Levodopa interacts with Boost with Testofen — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa, Levodopa interactionCarbidopa, Levodopa, EntacaponeStalevo
How Carbidopa, Levodopa, Entacapone interacts with Boost with Testofen — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa, Levodopa, Entacapone interactionLevodopaInbrija, Larodopa
How Levodopa interacts with Boost with Testofen — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Levodopa interactionLevodopa, CarbidopaDuodopa
How Levodopa, Carbidopa interacts with Boost with Testofen — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Levodopa, Carbidopa interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with Boost with Testofen — through 1 ingredient. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with Boost with Testofen — through 3 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Ado-trastuzumab Emtansine interactionHorny Goat Weed Leaf, Stem ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP3A4 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Ado-trastuzumab Emtansine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with Boost with Testofen — through 1 ingredient. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with Boost with Testofen — through 1 ingredient. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Abacavir, Lamivudine interactionAbciximabReoPro
How Abciximab interacts with Boost with Testofen — through 6 ingredients. Tap an ingredient for the detail:
NiacinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Niacin + Abciximab interactionL-arginineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, concomitant use of L-arginine with anticoagulant and antiplatelet drugs might have additive effects and increase the risk of bleeding.
Read the full L-arginine + Abciximab interactionTestofenAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, fenugreek might have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Testofen + Abciximab interactionHorny Goat Weed Leaf, Stem ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, horny goat weed might increase the risk of bleeding.
Read the full Horny Goat Weed Leaf, Stem Extract + Abciximab interactionBioperineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Bioperine + Abciximab interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with Boost with Testofen — through 3 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Abemaciclib interactionHorny Goat Weed Leaf, Stem ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP3A4 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Abemaciclib interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Abemaciclib interactionAbiraterone
How Abiraterone interacts with Boost with Testofen — through 4 ingredients. Tap an ingredient for the detail:
Horny Goat Weed Leaf, Stem ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP3A4 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Abiraterone interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Abiraterone interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Abiraterone interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with Boost with Testofen — through 4 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Abiraterone Acetate interactionHorny Goat Weed Leaf, Stem ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP3A4 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Abiraterone Acetate interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Abiraterone Acetate interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with Boost with Testofen — through 6 ingredients. Tap an ingredient for the detail:
NiacinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Niacin + Abrocitinib interactionL-arginineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, concomitant use of L-arginine with anticoagulant and antiplatelet drugs might have additive effects and increase the risk of bleeding.
Read the full L-arginine + Abrocitinib interactionBioperineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Bioperine + Abrocitinib interactionHorny Goat Weed Leaf, Stem ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, horny goat weed might increase the risk of bleeding.
Read the full Horny Goat Weed Leaf, Stem Extract + Abrocitinib interactionTestofenAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, fenugreek might have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Testofen + Abrocitinib interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with Boost with Testofen — through 3 ingredients. Tap an ingredient for the detail:
Horny Goat Weed Leaf, Stem ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP3A4 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Acalabrutinib interactionBioperineP-glycoprotein Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of P-glycoprotein substrates.
Read the full Bioperine + Acalabrutinib interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Boost with Testofen — through 4 ingredients. Tap an ingredient for the detail:
TestofenAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, fenugreek seed might have additive hypoglycemic effects when used with antidiabetes drugs.
Read the full Testofen + Acarbose interactionL-arginineAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, concomitant use of L-arginine might have additive effects with antidiabetes drugs.
Read the full L-arginine + Acarbose interactionNiacinAntidiabetes Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Niacin can increase blood glucose levels and may diminish the effects of antidiabetes drugs.
Read the full Niacin + Acarbose interactionBioperineAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Read the full Bioperine + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Boost with Testofen — through 5 ingredients. Tap an ingredient for the detail:
L-arginineAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, concomitant use of L-arginine and antihypertensive drugs may increase the risk of hypotension.
Read the full L-arginine + Acebutolol interactionHorny Goat Weed Leaf, Stem ExtractAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, horny goat weed might increase the risk of hypotension.
Read the full Horny Goat Weed Leaf, Stem Extract + Acebutolol interactionL-citrullineAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, concomitant use of L-citrulline with antihypertensive drugs might have additive effects and increase the chance of hypotension.
Read the full L-citrulline + Acebutolol interactionNiacinHepatotoxic Drugs, Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acebutolol interactionTestofenAntihypertensive Drugs Minor
Interaction Summary
Fenugreek may also have an additive effect on blood pressure-lowering medications.
Read the full Testofen + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Boost with Testofen — through 6 ingredients. Tap an ingredient for the detail:
L-arginineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, concomitant use of L-arginine with anticoagulant and antiplatelet drugs might have additive effects and increase the risk of bleeding.
Read the full L-arginine + Acenocoumarol interactionNiacinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Niacin + Acenocoumarol interactionHorny Goat Weed Leaf, Stem ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, horny goat weed might increase the risk of bleeding.
Read the full Horny Goat Weed Leaf, Stem Extract + Acenocoumarol interactionTestofenAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, fenugreek might have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Testofen + Acenocoumarol interactionBioperineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Bioperine + Acenocoumarol interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Acenocoumarol interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with Boost with Testofen — through 3 ingredients. Tap an ingredient for the detail:
Horny Goat Weed Leaf, Stem ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP1A2 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Acetaminophen interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen interactionBioperineCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with Boost with Testofen — through 6 ingredients. Tap an ingredient for the detail:
BioperineAnticoagulant/antiplatelet Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Bioperine + Acetaminophen, Aspirin interactionHorny Goat Weed Leaf, Stem ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP1A2 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Acetaminophen, Aspirin interactionTestofenAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, fenugreek might have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Testofen + Acetaminophen, Aspirin interactionNiacinHepatotoxic Drugs, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Aspirin interactionL-arginineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, concomitant use of L-arginine with anticoagulant and antiplatelet drugs might have additive effects and increase the risk of bleeding.
Read the full L-arginine + Acetaminophen, Aspirin interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with Boost with Testofen — through 7 ingredients. Tap an ingredient for the detail:
NiacinAspirin, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Large doses of aspirin might alter the clearance of niacin.
Read the full Niacin + Acetaminophen, Aspirin, Caffeine interactionL-arginineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, concomitant use of L-arginine with anticoagulant and antiplatelet drugs might have additive effects and increase the risk of bleeding.
Read the full L-arginine + Acetaminophen, Aspirin, Caffeine interactionTestofenAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, fenugreek might have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Testofen + Acetaminophen, Aspirin, Caffeine interactionHorny Goat Weed Leaf, Stem ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP1A2 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Acetaminophen, Aspirin, Caffeine interactionBioperineCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Aspirin, Caffeine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Aspirin, Caffeine interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with Boost with Testofen — through 3 ingredients. Tap an ingredient for the detail:
Horny Goat Weed Leaf, Stem ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP1A2 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionBioperineCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, ButalbitalAxocet, Bancap, Bucet, Butex Forte, Esgic CF, Orbivan CF +5 more
How Acetaminophen, Butalbital interacts with Boost with Testofen — through 3 ingredients. Tap an ingredient for the detail:
Horny Goat Weed Leaf, Stem ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP1A2 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Acetaminophen, Butalbital interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital interactionBioperineCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Butalbital interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with Boost with Testofen — through 4 ingredients. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital, Caffeine interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acetaminophen, Butalbital, Caffeine interactionHorny Goat Weed Leaf, Stem ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP1A2 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Acetaminophen, Butalbital, Caffeine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with Boost with Testofen — through 4 ingredients. Tap an ingredient for the detail:
Horny Goat Weed Leaf, Stem ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP3A4 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital, Caffeine, Codeine interactionBioperineCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with Boost with Testofen — through 3 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Bioperine + Acetaminophen, Butalbital, Codeine interactionHorny Goat Weed Leaf, Stem ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP1A2 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Acetaminophen, Butalbital, Codeine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with Boost with Testofen — through 3 ingredients. Tap an ingredient for the detail:
NiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital, Codeine Phosphate interactionBioperineCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Bioperine + Acetaminophen, Butalbital, Codeine Phosphate interactionHorny Goat Weed Leaf, Stem ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP1A2 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with Boost with Testofen — through 4 ingredients. Tap an ingredient for the detail:
Horny Goat Weed Leaf, Stem ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP1A2 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionBioperineCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Bioperine + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with Boost with Testofen — through 4 ingredients. Tap an ingredient for the detail:
BioperineCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Bioperine + Acetaminophen, Caffeine, Codeine interactionHorny Goat Weed Leaf, Stem ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, horny goat weed might increase the effects and side effects of CYP3A4 substrates.
Read the full Horny Goat Weed Leaf, Stem Extract + Acetaminophen, Caffeine, Codeine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Caffeine, Codeine interactionVitamin D3Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
Read the full Vitamin D3 + Acetaminophen, Caffeine, Codeine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Boost with Testofen with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Bioperine
Anticoagulant/Antiplatelet Drugs
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
In vitro research shows that piperine, a constituent of black pepper, seems to inhibit platelet aggregation. This has not been reported in humans.
Antidiabetes Drugs
Theoretically, black pepper might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Animal research shows that piperine, a constituent of black pepper, can reduce blood glucose levels. Monitor blood glucose levels closely. Dose adjustments might be necessary.
Atorvastatin (Lipitor)
Theoretically, black pepper might increase blood levels of atorvastatin.
Animal research shows that taking piperine, a constituent of black pepper, 35 mg/kg can increase the maximum serum concentration of atorvastatin three-fold. This has not been reported in humans.
Cyclosporine (Neoral, Sandimmune)
Theoretically, black pepper might increase the effects and side effects of cyclosporine.
In vitro research shows that piperine, a constituent of black pepper, increases the bioavailability of cyclosporine. This has not been reported in humans.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
In vitro research suggests that some constituents of black pepper inhibit CYP2D6. This has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
In vitro research and pharmacokinetic simulation data suggest that piperine, a constituent of black pepper, as well as the pepper fruit seem to inhibit CYP3A4. This has not been reported in humans.
Lithium
Theoretically, black pepper might increase blood levels of lithium due to its diuretic effects. The dose of lithium might need to be reduced.
Black pepper is thought to have diuretic properties.
Nevirapine (Viramune)
Black pepper might increase blood levels of nevirapine.
Clinical research shows that piperine, a constituent of black pepper, increases the plasma concentration of nevirapine. However, no adverse effects were observed in this study.
P-Glycoprotein Substrates
Theoretically, black pepper might increase levels of P-glycoprotein substrates.
In vitro research shows that piperine, a constituent of black pepper, seems to inhibit P-glycoprotein.
Pentobarbital (Nembutal)
Theoretically, black pepper might increase the sedative effects of pentobarbital.
Animal research shows that piperine, a constituent of black pepper, increases pentobarbital-induced sleeping time.
Phenytoin (Dilantin)
Black pepper might increase blood levels of phenytoin.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption, slow elimination, and increase levels of phenytoin. Taking a single dose of black pepper 1 gram along with phenytoin seems to double the serum concentration of phenytoin. Consuming a soup with black pepper providing piperine 44 mg/200 mL of soup along with phenytoin also seems to increase phenytoin levels when compared with consuming the same soup without black pepper.
Propranolol (Inderal)
Black pepper might increase blood levels of propranolol.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and slow elimination of propranolol.
Rifampin (Rifadin)
Black pepper might increase blood levels of rifampin.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and serum levels of rifampin.
Theophylline
Black pepper might increase blood levels of theophylline.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and slow elimination of theophylline.
Amoxicillin (Amoxil, Trimox)
Theoretically, black pepper might increase the effects and side effects of amoxicillin.
Animal research shows that taking piperine, a constituent of black pepper, with amoxicillin increases plasma levels of amoxicillin. This has not been reported in humans.
Carbamazepine (Tegretol)
Theoretically, black pepper might increase blood levels of carbamazepine, potentially increasing the effects and side effects of carbamazepine.
One clinical study in patients taking carbamazepine 300 mg or 500 mg twice daily shows that taking a single 20 mg dose of purified piperine, a constituent of black pepper, increases carbamazepine levels. Piperine may increase carbamazepine absorption by increasing blood flow to the GI tract, increasing the surface area of the small intestine, or inhibiting cytochrome P450 3A4 (CYP3A4) in the gut wall. Absorption was significantly increased by 7-10 mcg/mL/hour. The time to eliminate carbamazepine was also increased by 4-8 hours. Although carbamazepine levels were increased, this did not appear to increase side effects. In vitro research also shows that piperine can increase carbamazepine levels by 11% in a time-dependent manner.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
In vitro research suggests that black pepper induces CYP1A2. This has not been reported in humans.
Horny Goat Weed Leaf, Stem Extract
Anticoagulant/Antiplatelet Drugs
Theoretically, horny goat weed might increase the risk of bleeding.
In vitro research and animal research shows that horny goat weed can inhibit platelet aggregation and thrombus formation. This effect has not been reported in humans.
Antihypertensive Drugs
Theoretically, horny goat weed might increase the risk of hypotension.
Laboratory research suggests that horny goat weed might have hypotensive effects. This effect has not been reported in humans.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, horny goat weed might increase the effects and side effects of CYP1A2 substrates.
In vitro, horny goat weed leaf extract inhibits CYP1A2. This effect has not been reported in humans.
Cytochrome P450 2B6 (Cyp2B6) Substrates
Theoretically, horny goat weed might increase the effects and side effects of CYP2B6 substrates.
In vitro, horny goat weed leaf extract inhibits CYP2B6. This effect has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, horny goat weed might increase the effects and side effects of CYP3A4 substrates.
In vitro, horny goat weed extract inhibits CYP3A4 and suppresses CYP3A4 mRNA expression. This effect has not been reported in humans.
Estrogens
Theoretically, concomitant use of horny goat weed with estrogens might increase their therapeutic and adverse effects.
In vitro evidence suggests that horny goat weed has estrogenic activity. In clinical research, horny goat weed has been shown to increase blood levels of estrogen in some females.
Niacin
Alcohol (Ethanol)
Concomitant use of alcohol and niacin might increase the risk of flushing and hepatotoxicity.
Alcohol can exacerbate the flushing and pruritus associated with niacin. Large doses of niacin might also exacerbate liver dysfunction associated with chronic alcohol use. A case report describes delirium and lactic acidosis in a patient taking niacin 3 grams daily who ingested 1 liter of wine. Advise patients to avoid large amounts of alcohol while taking niacin.
Allopurinol (Zyloprim)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as allopurinol.
Large doses of niacin can reduce urinary excretion of uric acid, potentially resulting in hyperuricemia. Doses of uricosurics such as allopurinol might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Anticoagulant/Antiplatelet Drugs
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Several cases of clotting factor synthesis deficiency and coagulopathy have been reported in patients taking sustained-release niacin. Also, thrombocytopenia has been reported in patients treated with niacin or niacin plus lovastatin.
Antidiabetes Drugs
Niacin can increase blood glucose levels and may diminish the effects of antidiabetes drugs.
Niacin impairs glucose tolerance in a dose-dependent manner, probably by causing or aggravating insulin resistance and increasing hepatic production of glucose. In diabetes patients, niacin 4.5 grams daily for 5 weeks can increase plasma glucose by an average of 16% and glycated hemoglobin (HbA1c) by 21%. However, lower doses of 1.5 grams daily or less appear to have minimal effects on blood glucose. In some patients, glucose levels increase when niacin is started, but then return to baseline when a stable dose is reached. Up to 35% of patients with diabetes may need adjustments in hypoglycemic therapy when niacin is added.
Antihypertensive Drugs
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
The vasodilating effects of niacin can cause hypotension. Furthermore, some clinical evidence suggests that a one-hour infusion of niacin can reduce systolic, diastolic, and mean blood pressure in hypertensive patients. This effect is not observed in normotensive patients.
Bile Acid Sequestrants
Bile acid sequestrants can bind niacin and decrease absorption. Separate administration by 4-6 hours to avoid an interaction.
In vitro studies show that colestipol (Colestid) binds about 98% of available niacin and cholestyramine (Questran) binds 10% to 30%.
Gemfibrozil (Lopid)
Theoretically, concomitant use of niacin and gemfibrozil might increase the risk of myopathy in some patients.
A case of myopathy from concomitant use of niacin and gemfibrozil has been reported. Niacin alone has also been associated with cases of myopathy. Using gemfibrozil with niacin might further increase the risk of developing myopathy.
Hepatotoxic Drugs
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Niacin has been associated with cases of liver toxicity, especially when used in pharmacologic doses. Sustained-release niacin preparations appear to be associated with a higher risk of hepatotoxicity than immediate-release niacin.
Hmg-Coa Reductase Inhibitors ("Statins")
Theoretically, concomitant use of niacin and statins might increase the risk of myopathy and rhabdomyolysis in some patients.
Some case reports have raised concerns that niacin might increase the risk of myopathy and rhabdomyolysis when combined with statins. However, a significantly increased risk of myopathy has not been demonstrated in clinical trials, including those using an FDA-approved combination of lovastatin and niacin (Advicor).
Probenecid (Benemid)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as probenecid.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as probenecid might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Sulfinpyrazone (Anturane)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as sulfinpyrazone.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as sulfinpyrazone might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Thyroid Hormone
Theoretically, niacin might antagonize the therapeutic effects of thyroid hormones.
Clinical research and case reports suggests that taking niacin can reduce serum levels of thyroxine-binding globulin by up to 25% and moderately reduce levels of thyroxine (T4). Patients taking thyroid hormone for hypothyroidism might need dose adjustments when using niacin.
Transdermal Nicotine (Nicoderm)
Theoretically, concomitant use of niacin and transdermal nicotine might increase the risk of flushing and dizziness.
Niacin and nicotine can both cause flushing and dizziness.
Warfarin (Coumadin)
There is limited evidence that niacin may increase the anticoagulant effects of warfarin.
In a case report, a patient on warfarin developed an elevated international normalized ratio (INR) of 3.9 after taking niacin for two weeks. The patient's INR was previously stable, ranging between 2 and 3 in recent months, and no other medication changes were identified. The elevated INR returned to therapeutic range within 4 days following the discontinuation of niacin.
Aspirin
Large doses of aspirin might alter the clearance of niacin.
Aspirin is often used with niacin to reduce niacin-induced flushing. Doses of 80-975 mg aspirin have been used, but 325 mg appears to be optimal. Aspirin also seems to reduce the clearance of niacin by competing for glycine conjugation. Taking aspirin 1 gram seems to reduce niacin clearance by 45%. This is probably a dose-related effect and not clinically significant with the more common aspirin dose of 325 mg.
Vitamin D3
Aluminum
Vitamin D might increase aluminum absorption and toxicity, but this has only been reported in people with renal failure.
The protein that transports calcium across the intestinal wall can also bind and transport aluminum. This protein is stimulated by vitamin D, which may therefore increase aluminum absorption. This mechanism may contribute to increased aluminum levels and toxicity in people with renal failure, when they take vitamin D and aluminum-containing phosphate binders chronically.
Atorvastatin (Lipitor)
Vitamin D might reduce absorption of atorvastatin.
A small, low-quality clinical study shows that taking vitamin D reduces levels of atorvastatin and its active metabolites by up to 55%. However, while atorvastatin levels decreased, total cholesterol, low-density lipoprotein (LDL) cholesterol, and high-density lipoprotein (HDL) cholesterol levels did not substantially change. Atorvastatin is metabolized in the gut by CYP3A4 enzymes, and researchers theorized that vitamin D might induce CYP3A4, causing reduced levels of atorvastatin. However, this proposed mechanism was not specifically studied.
Calcipotriene (Dovonex)
Taking calcipotriene with vitamin D increases the risk for hypercalcemia.
Calcipotriene is a vitamin D analog used topically for psoriasis. It can be absorbed in sufficient amounts to cause systemic effects, including hypercalcemia. Theoretically, combining calcipotriene with vitamin D supplements might increase the risk of hypercalcemia.
Digoxin (Lanoxin)
Theoretically, hypercalcemia induced by high-dose vitamin D can increase the risk of arrhythmia from digoxin.
High doses of vitamin D can cause hypercalcemia. Hypercalcemia increases the risk of fatal cardiac arrhythmias with digoxin. Avoid vitamin D doses above the tolerable upper intake level (4000 IU daily for adults) and monitor serum calcium levels in people taking vitamin D and digoxin concurrently.
Diltiazem (Cardizem, Others)
Theoretically, hypercalcemia induced by high-dose vitamin D can reduce the therapeutic effects of diltiazem for arrhythmia.
High doses of vitamin D can cause hypercalcemia. Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically this could also occur with diltiazem. Avoid vitamin D doses above the tolerable upper intake level (4000 IU daily for adults) and monitor serum calcium levels in people taking vitamin D and diltiazem concurrently.
Thiazide Diuretics
Theoretically, taking thiazide diuretics and high-dose vitamin D can increase the risk of hypercalcemia.
Thiazide diuretics decrease urinary calcium excretion, which could lead to hypercalcemia if vitamin D supplements are taken concurrently. This has been reported in people being treated with vitamin D for hypoparathyroidism, and also in elderly people with normal parathyroid function who were taking a thiazide, vitamin D, and calcium-containing antacids daily.
Verapamil (Calan, Others)
Hypercalcemia induced by high-dose vitamin D can reduce the therapeutic effects of verapamil for arrhythmia.
Hypercalcemia due to high doses of vitamin D can reduce the effectiveness of verapamil in atrial fibrillation. Avoid vitamin D doses above the tolerable upper intake level (4000 IU daily for adults) and monitor serum calcium levels in people taking vitamin D and verapamil concurrently.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Vitamin D might induce CYP3A4 enzymes and reduce the bioavailability of CYP3A4 substrates.
There is some concern that vitamin D might induce CYP3A4. In vitro research suggests that vitamin D induces CYP3A4 transcription. Additionally, observational research has found that increased UV light exposure and serum vitamin D levels are associated with decreased serum levels of CYP3A4 substrates such as tacrolimus and sirolimus, while no association between UV light exposure or vitamin D levels and levels of mycophenolic acid, a non-CYP3A4 substrate, was found. A small, low-quality clinical study shows that taking vitamin D reduces levels of the CYP3A4 substrate atorvastatin and its active metabolites by up to 55%; however, the clinical effects of atorvastatin were not reduced. While researchers theorized that vitamin D might induce CYP3A4, this proposed mechanism was not specifically studied.
L-Arginine
Ace Inhibitors (Aceis)
Theoretically, concomitant use of L-arginine and ACE inhibitors may increase the risk for hypotension and hyperkalemia.
Combining L-arginine with some antihypertensive drugs, especially ACE inhibitors, seems to have additive vasodilating and blood pressure-lowering effects. Furthermore, ACE inhibitors can increase potassium levels. Use of L-arginine has been associated with hyperkalemia in some patients. Theoretically, concomitant use of ACE inhibitors with L-arginine may increases the risk of hyperkalemia.
Angiotensin Receptor Blockers (Arbs)
Theoretically, concomitant use of L-arginine and ARBs may increase the risk of hypotension and hyperkalemia.
L-arginine increases nitric oxide, which causes vasodilation. Combining L-arginine with ARBs seems to increase L-arginine-induced vasodilation. Furthermore, ARBs can increase potassium levels. Use of L-arginine has been associated with hyperkalemia in some patients. Theoretically, concomitant use of ARBs with L-arginine may increases the risk of hyperkalemia.
Anticoagulant/Antiplatelet Drugs
Theoretically, concomitant use of L-arginine with anticoagulant and antiplatelet drugs might have additive effects and increase the risk of bleeding.
Preliminary research suggests that L-arginine infusions reduce platelet aggregation in humans. The clinical significance of this effect is unclear.
Antidiabetes Drugs
Theoretically, concomitant use of L-arginine might have additive effects with antidiabetes drugs.
Preliminary clinical research shows that L-arginine decreases blood glucose levels in patients with type 2 diabetes.
Antihypertensive Drugs
Theoretically, concomitant use of L-arginine and antihypertensive drugs may increase the risk of hypotension.
L-arginine increases nitric oxide, which causes vasodilation. Clinical evidence shows that L-arginine can reduce blood pressure in some individuals with hypertension. Furthermore, combining L-arginine with some antihypertensive drugs seems to have additive vasodilating and blood pressure-lowering effects.
Isoproterenol (Isuprel)
Theoretically, concurrent use of isoproterenol and L-arginine might result in additive effects and hypotension.
Preliminary clinical evidence suggests that L-arginine enhances isoproterenol-induced vasodilation in patients with essential hypertension or a family history of essential hypertension.
Potassium-Sparing Diuretics
Theoretically concomitant use of potassium-sparing diuretics with L-arginine may increases the risk of hyperkalemia.
Potassium-sparing diuretics can increase potassium levels. Use of L-arginine has been associated with hyperkalemia in some patients.
Sildenafil (Viagra)
Theoretically, concurrent use of sildenafil and L-arginine might increase the risk for hypotension.
In vivo, concurrent use of L-arginine and sildenafil has resulted in increased vasodilation. Theoretically, concurrent use might have additive vasodilatory and hypotensive effects. However, in studies evaluating the combined use of L-arginine and sildenafil for erectile dysfunction, hypotension was not reported.
Testosterone
Theoretically, concomitant use of L-arginine and testosterone might have additive effects.
In clinical research, L-arginine increases the level of testosterone in male patients with erectile dysfunction. The clinical significance of this finding is unclear.
Testofen
Anticoagulant/Antiplatelet Drugs
Theoretically, fenugreek might have additive effects when used with anticoagulant or antiplatelet drugs.
Some of the constituents in fenugreek have antiplatelet effects in animal and in vitro research. However, common fenugreek products might not contain sufficient concentrations of these constituents for clinical effects. A clinical study in patients with coronary artery disease or diabetes shows that taking fenugreek seed powder 2.5 grams twice daily for 3 months does not affect platelet aggregation, fibrinolytic activity, or fibrinogen levels .
Antidiabetes Drugs
Theoretically, fenugreek seed might have additive hypoglycemic effects when used with antidiabetes drugs.
Clinical research shows that fenugreek seed can reduce fasting blood glucose and 2-hour postprandial glucose levels in adults with type 2 diabetes.
Clopidogrel (Plavix)
Theoretically, fenugreek seed might alter the clinical effects of clopidogrel by inhibiting its conversion to the active form.
Animal research shows that fenugreek seed 200 mg/kg daily for 14 days increases the maximum serum concentration of clopidogrel by 21%. It is unclear how this affects the pharmacokinetics of the active metabolite of clopidogrel; however, this study found that concomitant use of fenugreek seed and clopidogrel prolonged bleeding time by an additional 11%.
Metoprolol (Toprol)
Theoretically, fenugreek seed might have additive hypotensive effects when used with metoprolol.
Animal research shows that fenugreek seed 300 mg/kg daily for 2 weeks decreases systolic and diastolic blood pressure by 9% and 11%, respectively, when administered alone, and by 15% and 22%, respectively, when given with metoprolol 10 mg/kg.
Phenytoin (Dilantin)
Theoretically, fenugreek might decrease plasma levels of phenytoin.
Animal research shows that taking fenugreek seeds for 1 week decreases maximum concentrations and the area under the curve of a single dose of phenytoin by 44% and 72%, respectively. This seems to be related to increased clearance. So far, this interaction has not been reported in humans.
Sildenafil (Viagra)
Theoretically, concurrent use of sildenafil and fenugreek might reduce levels and therapeutic effects of sildenafil.
Animal research shows that taking fenugreek seeds for 1 week reduces maximum concentrations and the area under the curve of a single dose of sildenafil by 27% and 48%, respectively. So far, this interaction has not been reported in humans.
Theophylline
Theoretically, fenugreek may reduce the levels and clinical effects of theophylline.
Animal research shows that fenugreek 50 grams daily for 7 days reduces the maximum serum concentration (Cmax) of theophylline by 28% and the area under the plasma drug concentration-time curve (AUC) by 22%.
Warfarin (Coumadin)
Theoretically, fenugreek might have additive effects with warfarin and increase the international normalized ratio (INR).
Some fenugreek constituents have antiplatelet effects, although these might not be present in concentrations that are clinically significant. In one case report, a patient taking warfarin experienced an increased INR when starting to take fenugreek in combination with boldo.
Antihypertensive Drugs
Fenugreek may also have an additive effect on blood pressure-lowering medications. Studies on animals have shown that fenugreek seed can decrease both systolic and diastolic blood pressure by up to 22% when combined with metoprolol. Therefore, it is essential to monitor your blood pressure regularly if you are taking fenugreek and metoprolol together or any other antihypertensive drugs.
Magnesium
Levodopa/Carbidopa (Sinemet)
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Clinical research in healthy volunteers shows that taking magnesium oxide 1000 mg with levodopa 100 mg/carbidopa 10 mg reduces the area under the curve (AUC) of levodopa by 35% and of carbidopa by 81%. In vitro and animal research shows that magnesium produces an alkaline environment in the digestive tract, which might lead to degradation and reduced bioavailability of levodopa/carbidopa.
Aminoglycoside Antibiotics
Concomitant use of aminoglycoside antibiotics and magnesium can increase the risk for neuromuscular weakness.
Both aminoglycosides and magnesium reduce presynaptic acetylcholine release, which can lead to neuromuscular blockade and possible paralysis. This is most likely to occur with high doses of magnesium given intravenously.
Antacids
Use of acid reducers may reduce the laxative effect of magnesium oxide.
A retrospective analysis shows that, in the presence of H2 receptor antagonists (H2RAs) or proton pump inhibitors (PPIs), a higher dose of magnesium oxide is needed for a laxative effect. This may also occur with antacids. Under acidic conditions, magnesium oxide is converted to magnesium chloride and then to magnesium bicarbonate, which has an osmotic laxative effect. By reducing acidity, antacids may reduce the conversion of magnesium oxide to the active bicarbonate salt.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after magnesium containing products.
Bisphosphonates
Magnesium can decrease absorption of bisphosphonates.
Cations, including magnesium, can decrease bisphosphonate absorption. Advise patients to separate doses of magnesium and these drugs by at least 2 hours.
Calcium Channel Blockers
Magnesium can have additive effects with calcium channel blockers, although evidence is conflicting.
Magnesium inhibits calcium entry into smooth muscle cells and may therefore have additive effects with calcium channel blockers. Severe hypotension and neuromuscular blockades may occur when nifedipine is used with intravenous magnesium, although some contradictory evidence suggests that concurrent use of magnesium with nifedipine does not increase the risk of neuromuscular weakness. High doses of magnesium could theoretically have additive effects with other calcium channel blockers.
Digoxin
Magnesium salts may reduce absorption of digoxin.
Clinical evidence suggests that treatment with oral magnesium hydroxide or magnesium trisilicate reduces absorption of digoxin from the intestines. This may reduce the blood levels of digoxin and decrease its therapeutic effects.
Potassium-Sparing Diuretics
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Potassium-sparing diuretics also have magnesium-sparing properties, which can counteract the magnesium losses associated with loop and thiazide diuretics. Theoretically, increased magnesium levels could result from concomitant use of potassium-sparing diuretics and magnesium supplements.
Quinolone Antibiotics
Magnesium decreases absorption of quinolones.
Magnesium can form insoluble complexes with quinolones and decrease their absorption. Advise patients to take these drugs at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Skeletal Muscle Relaxants
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Parenteral magnesium shortens the time to onset of skeletal muscle relaxants by about 1 minute and prolongs the duration of action by about 2 minutes. Magnesium potentiates the effects of skeletal muscle relaxants by decreasing calcium-mediated release of acetylcholine from presynaptic nerve terminals, reducing postsynaptic sensitivity to acetylcholine, and having a direct effect on the membrane potential of myocytes. Magnesium also has vasodilatory actions and increases cardiac output, allowing a greater amount of muscle relaxant to reach the motor end plate. A clinical study found that low-dose rocuronium (0.45 mg/kg), when given after administration of magnesium 30 mg/kg over 10 minutes, has an accelerated onset of effect, which matches the onset of effect seen with a full-dose rocuronium regimen (0.6 mg/kg). In another clinical study, onset times for rocuronium doses of 0.3, 0.6, and 1.2 mg/kg were 86, 76, and 50 seconds, respectively, when given alone, but were reduced to 66, 44, and 38 seconds, respectively, when the doses were given after a 15-minute infusion of magnesium sulfate 60 mg/kg. Giving intraoperative intravenous magnesium sulfate, 50 mg/kg loading dose followed by 15 mg/kg/hour, reduces the onset time of rocuronium, enhances its clinical effects, reduces the dose of intraoperative opiates, and prolongs the spontaneous recovery time. It does not affect the activity of subsequently administered neostigmine.
Sulfonylureas
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Clinical research shows that administration of magnesium hydroxide with glyburide increases glyburide absorption, increases maximal insulin response by 35-fold, and increases the risk of hypoglycemia, when compared with glyburide alone. A similar interaction occurs between magnesium hydroxide and glipizide. The mechanism of this effect appears to be related to the elevation of gastrointestinal pH by magnesium-based antacids, increasing solubility and enhancing absorption of sulfonylureas.
Tetracycline Antibiotics
Magnesium decreases absorption of tetracyclines.
Magnesium can form insoluble complexes with tetracyclines in the gut and decrease their absorption and antibacterial activity. Advise patients to take these drugs 1 hour before or 2 hours after magnesium supplements.
Anticoagulant/Antiplatelet Drugs
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
In vitro evidence shows that magnesium sulfate inhibits platelet aggregation, even at low concentrations. Some preliminary clinical evidence shows that infusion of magnesium sulfate increases bleeding time by 48% and reduces platelet activity. However, other clinical research shows that magnesium does not affect platelet aggregation, although inhibition of platelet-dependent thrombosis can occur.
Gabapentin (Neurontin)
Gabapentin absorption can be decreased by magnesium.
Clinical research shows that giving magnesium oxide orally along with gabapentin decreases the maximum plasma concentration of gabapentin by 33%, time to maximum concentration by 36%, and area under the curve by 43%. Advise patients to take gabapentin at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Sevelamer (Renagel, Renvela)
Sevelamer may increase serum magnesium levels.
In patients on hemodialysis, sevelamer use was associated with a 0.28 mg/dL increase in serum magnesium. The mechanism of this interaction remains unclear.
L-Citrulline
Antihypertensive Drugs
Theoretically, concomitant use of L-citrulline with antihypertensive drugs might have additive effects and increase the chance of hypotension.
L-citrulline is converted to L-arginine, which can increase nitric oxide and cause vasodilation. However, a meta-analysis of 5 small clinical studies suggests that taking L-citrulline 3-6 grams daily for 1-8 weeks does not lower blood pressure when compared with control.
Phosphodiesterase-5 Inhibitors
Theoretically, concurrent use of phosphodiesterase-5 (PDE-5) inhibitors and L-citrulline might result in additive vasodilation.
L-citrulline is converted to L-arginine, which can increase nitric oxide and cause vasodilation. Theoretically, taking L-arginine with PDE-5 inhibitors might have additive vasodilatory and hypotensive effects. However, in studies evaluating the combined use of L-arginine and sildenafil for erectile dysfunction, hypotension was not reported.
Zinc
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Theoretically, zinc might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after zinc containing products.
Cephalexin (Keflex)
Zinc might decrease cephalexin levels by chelating with cephalexin in the gut and preventing its absorption.
A pharmacokinetic study shows that zinc sulfate 250 mg taken concomitantly with cephalexin 500 mg decreases peak levels of cephalexin by 31% and reduces the exposure to cephalexin by 27%. Also, taking zinc sulfate 3 hours before cephalexin decreases peak levels of cephalexin by 11% and reduces the exposure to cephalexin by 18%. By decreasing cephalexin levels, zinc might increase the risk of treatment failure. This effect does not occur when zinc is taken 3 hours after the cephalexin dose. To avoid an interaction, advise patients take zinc sulfate 3 hours after taking cephalexin.
Cisplatin (Platinol-Aq)
Theoretically, zinc might interfere with the therapeutic effects of cisplatin.
Animal research suggests that zinc stimulates tumor cell production of the protein metallothionein, which binds and inactivates cisplatin. It is not known whether zinc supplements or high dietary zinc intake can cause clinically significant interference with cisplatin therapy. Cisplatin might also increase zinc excretion.
Integrase Inhibitors
Theoretically, taking zinc along with integrase inhibitors might decrease the levels and clinical effects of these drugs.
Zinc is a divalent cation. Pharmacokinetic studies have shown that other divalent cations such as calcium and iron can decrease blood levels of the integrase inhibitor dolutegravir through chelation.
Penicillamine (Cuprimine, Depen)
Zinc might reduce the levels and clinical effects of penicillamine.
By forming an insoluble complex with penicillamine, zinc interferes with penicillamine absorption and activity. Zinc supplements reduce the efficacy of low-dose penicillamine (0.5-1 gram/day), but do not seem to affect higher doses (1-2.75 gram/day), provided dosing times are separated. Advise patients to take zinc and penicillamine at least 2 hours apart.
Quinolone Antibiotics
Zinc can decrease the levels and clinical effects of quinolones antibiotics.
Quinolones form complexes with zinc in the gastrointestinal tract, reducing absorption of both the quinolone and zinc if taken at the same time. Advise patients to take these drugs at least 2 hours before, or 4-6 hours after, zinc supplements.
Ritonavir (Norvir)
Zinc modestly reduces levels of ritonavir.
Clinical research shows that zinc might reduce serum ritonavir levels by chelating with ritonavir in the gut and preventing its absorption. In patients with HIV, ritonavir is taken with atazanavir to prevent the metabolism and increase the effects of atazanavir. A pharmacokinetic study shows that, in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate (Solvazinc tablets) 125 mg as a single dose or as multiple daily doses for 2 weeks reduces plasma levels of ritonavir by about 16%. However, atazanavir levels still remains high enough to prevent HIV virus replication. Therefore, the decrease in ritonavir levels is not likely to be clinically significant.
Tetracycline Antibiotics
Zinc might reduce levels of tetracycline antibiotics.
Tetracyclines form complexes with zinc in the gastrointestinal tract, which can reduce absorption of both the tetracycline and zinc when taken at the same time. Taking zinc sulfate 200 mg with tetracycline reduces absorption of the antibiotic by 30% to 40%. Demeclocycline and minocycline cause a similar interaction. However, doxycycline does not seem to interact significantly with zinc. Advise patients to take tetracyclines at least 2 hours before, or 4-6 hours after, zinc supplements to avoid any interactions.
Amiloride (Midamor)
Amiloride can modestly reduce zinc excretion and increase zinc levels.
Clinical research shows that amiloride can reduce urinary zinc excretion, especially at doses of 10 mg per day or more. This zinc-sparing effect can help to counteract zinc losses caused by thiazide diuretics, but it is unlikely to cause zinc toxicity at usual amiloride doses. The other potassium-sparing diuretics, spironolactone (Aldactone) and triamterene (Dyrenium), do not seem to have a zinc-sparing effect.
Atazanavir (Reyataz)
Zinc modestly reduces levels of atazanavir, although this effect does not seem to be clinically significant.
Clinical research shows that zinc might decrease serum atazanavir levels by chelating with atazanavir in the gut and preventing its absorption. Although a single dose of zinc sulfate (Solvazinc tablets) 125 mg orally does not affect atazanavir concentrations in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate 125 mg daily for 2 weeks reduces plasma levels of atazanavir by about 22% in these patients. However, despite this decrease, atazanavir levels still remain at high enough concentrations for the prevention of HIV virus replication.
Vitamin B12
Metformin (Glucophage)
Metformin, a common medication used to manage type 2 diabetes, has been associated with lower vitamin B12 levels in some individuals. Prolonged use of metformin can interfere with the absorption of B12 in the digestive system, potentially leading to a deficiency in this essential vitamin.
Brand information
Manufacturer and brand details for Boost with Testofen, from the product label.
Trojan Man
See all Trojan Man products- Name
- Church & Dwight Co., Inc.
- City
- Ewing
- State
- NJ
- ZipCode
- 08628
- Phone Number
- 1-877-320-3075
Boost with Testofen by Trojan Man: Common Questions
Does Boost with Testofen by Trojan Man interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Is this safe to take if I'm pregnant or breastfeeding?
What does L-arginine do in this product?
Why is magnesium in a testosterone supplement?
What are the most common side effects I might notice?
Does this product work for boosting testosterone?
Can I take this with my blood pressure medication?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Boost with Testofen is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Boost with Testofen’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin D
Interacts with 715 drugsVitamin D is a fat-soluble vitamin that helps your body absorb calcium and is important for healthy bones, muscles, and immune function. Many people, especially those with low sun exposure,...
Read the full Vitamin D monograph → Herb & supplement monographZinc
Interacts with 67 drugsZinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but supplements can help correct or prevent a defici...
Read the full Zinc monograph → Herb & supplement monographNiacin
Interacts with 727 drugsNiacin (vitamin B3) is an essential nutrient your body needs for energy and metabolism, and deficiency is uncommon in most developed countries. Prescription-strength niacin has been used to...
Read the full Niacin monograph → Herb & supplement monographVitamin B12
Interacts with 20 drugsVitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very helpful for people who are deficient — su...
Read the full Vitamin B12 monograph → Herb & supplement monographMagnesium
Interacts with 295 drugsMagnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preventing or correcting deficiency. Some othe...
Read the full Magnesium monograph → Herb & supplement monographL-arginine
Interacts with 403 drugsL-arginine is an amino acid that the body uses to make nitric oxide, a substance that helps blood vessels relax and widen. It is popularly used for blood pressure, erectile dysfunction, and...
Read the full L-arginine monograph → Herb & supplement monographL-citrulline
Interacts with 178 drugsL-citrulline is an amino acid that the body turns into L-arginine to help make nitric oxide, which relaxes blood vessels and may improve blood flow. It is popular for exercise performance an...
Read the full L-citrulline monograph → Herb & supplement monographBlack Pepper
Interacts with 1,019 drugsBlack pepper is a common kitchen spice that is generally safe in the amounts used in food. Its extract, piperine, is mostly added to supplements to help the body absorb other ingredients (li...
Read the full Black Pepper monograph → Herb & supplement monographFenugreek
Interacts with 389 drugsFenugreek is a common kitchen spice that is also taken as a supplement, mainly for blood sugar, cholesterol, and to support breast milk production. Some early research is encouraging for blo...
Read the full Fenugreek monograph → Herb & supplement monographHorny Goat Weed
Interacts with 963 drugsHorny goat weed (Epimedium) is a traditional Chinese herb most often marketed for low libido and erectile problems, but solid human evidence for these uses is lacking. While short-term use s...
Read the full Horny Goat Weed monograph →Sources & How We Checked
Boost with Testofen's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 436 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
L-arginine 66 references
- Sapienza MA, Kharitonov SA, Horvath I, et al. Effect of inhaled L-arginine on exhaled nitric oxide in normal and asthmatic subjects. Thorax 1998;53:172-5.
- Clarkson P, Adams MR, Powe AJ, et al. Oral L-arginine improves endothelium-dependent dilation in hypercholesterolemic young adults. J Clin Invest 1996;97:1989-94. PubMed
- Tenenbaum A, Fisman EZ, Motro M. L-arginine: Rediscovery in progress. Cardiology 1998;90:153-9.
- Brittenden J, Park KGM, Heys SD, et al. L-Arginine stimulates host defenses in patients with breast cancer. Surgery 1994;115:205-12.
- Korting GE, Smith SD, Wheeler MA, et al. A randomized double-blind trial of oral L-arginine for treatment of interstitial cystitis. J Urol 1999;161:558-65. DOI
- Rector TS, Bank AJ, Mullen KA, et al. Randomized, double-blind, placebo-controlled study of supplemental oral L-arginine in patients with heart failure. Circulation 1996;93:2135-41.
- Siani A, Pagano E, Iacone R, et al. Blood pressure and metabolic changes during dietary L-arginine supplementation in humans. Am J Hypertens 2000;13:547-51. PubMed
- Cheng JW, Balwin SN. L-arginine in the management of cardiovascular diseases. Ann Pharmacother 2001;35:755-64. PubMed
- Wallace AW, Tom WL. Interaction of L-arginine and phosphodiesterase inhibitors in vasodilation of the porcine internal mammary artery. Anesth Analg 2000;90:840-6. DOI
- Huynh NT, Tayek JA. Oral arginine reduces systemic blood pressure in type 2 diabetes: its potential role in nitric oxide generation. J Am Coll Nutr 2002;21:422-7.. PubMed
- Staff AC, Berge L, Haugen G, et al. Dietary supplementation with L-arginine or placebo in women with pre-eclampsia. Acta Obstet Gynecol Scand 2004;83:103-7.
- Resnick DJ, Softness B, Murphy AR, et al. Case report of an anaphylactoid reaction to arginine. Ann Allergy Asthma Immunol 2002;88:67-8. PubMed
- Anon. Arginine hydrochloride injection (marketed as R-Gene 10). FDA Drug Safety Newsletter 2009;2(2):16-18. Available at: www.fda.gov/Drugs/DrugSafety/DrugSafetyNewsletter/default.htm.
- Higashi Y, Oshima T, Sasaki S, et. al. Angiotensin-converting enzyme inhibition, but not calcium antagonism, improves a response of the renal vasculature to L-arginine in patients with essential hypertension. Hypertension. 1998 Jul;32(1):16-24.
- Facchinetti, F., Longo, M., Piccinini, F., Neri, I., and Volpe, A. L-arginine infusion reduces blood pressure in preeclamptic women through nitric oxide release. J Soc Gynecol.Investig. 1999;6(4):202-207. DOI
- de Gouw, H. W., Verbruggen, M. B., Twiss, I. M., and Sterk, P. J. Effect of oral L-arginine on airway hyperresponsiveness to histamine in asthma. Thorax 1999;54(11):1033-1035. PubMed
- Komers, R., Komersova, K., Kazdova, L., Ruzickova, J., and Pelikanova, T. Effect of ACE inhibition and angiotensin AT1 receptor blockade on renal and blood pressure response to L-arginine in humans. J Hypertens. 2000;18(1):51-59. PubMed
- Cartledge, J. J., Davies, A. M., and Eardley, I. A randomized double-blind placebo-controlled crossover trial of the efficacy of L-arginine in the treatment of interstitial cystitis. BJU.Int. 2000;85(4):421-426.
- Sozykin, A. V., Noeva, E. A., Balakhonova, T. V., Pogorelova, O. A., and Men'shikov, M. I. [Effect of L-arginine on platelet aggregation, endothelial function adn exercise tolerance in patients with stable angina pectoris]. Ter.Arkh. 2000;72(8):24-27.
- Nagaya, N., Uematsu, M., Oya, H., Sato, N., Sakamaki, F., Kyotani, S., Ueno, K., Nakanishi, N., Yamagishi, M., and Miyatake, K. Short-term oral administration of L-arginine improves hemodynamics and exercise capacity in patients with precapillary pulmona
- Stokes, G. S., Barin, E. S., Gilfillan, K. L., and Kaesemeyer, W. H. Interactions of L-arginine, isosorbide mononitrate, and angiotensin II inhibitors on arterial pulse wave. Am J Hypertens. 2003;16(9 Pt 1):719-724.
- Park, K. G., Heys, S. D., Blessing, K., Kelly, P., McNurlan, M. A., Eremin, O., and Garlick, P. J. Stimulation of human breast cancers by dietary L-arginine. Clin.Sci.(Lond) 1992;82(4):413-417.
- Palloshi, A., Fragasso, G., Piatti, P., Monti, L. D., Setola, E., Valsecchi, G., Galluccio, E., Chierchia, S. L., and Margonato, A. Effect of oral L-arginine on blood pressure and symptoms and endothelial function in patients with systemic hypertension,
- Schlaich, M. P., Ahlers, B. A., Parnell, M. M., and Kaye, D. M. beta-Adrenoceptor-mediated, nitric-oxide-dependent vasodilatation is abnormal in early hypertension: restoration by L-arginine. J Hypertens. 2004;22(10):1917-1925. PubMed
- Neri, I., Blasi, I., and Facchinetti, F. Effects of acute L-arginine infusion on non-stress test in hypertensive pregnant women. J Matern.Fetal Neonatal Med. 2004;16(1):23-26. PubMed
- Rytlewski, K., Olszanecki, R., Korbut, R., and Zdebski, Z. Effects of prolonged oral supplementation with l-arginine on blood pressure and nitric oxide synthesis in preeclampsia. Eur.J Clin.Invest 2005;35(1):32-37.
- Mansoor, J. K., Morrissey, B. M., Walby, W. F., Yoneda, K. Y., Juarez, M., Kajekar, R., Severinghaus, J. W., Eldridge, M. W., and Schelegle, E. S. L-arginine supplementation enhances exhaled NO, breath condensate VEGF, and headache at 4,342 m. High Alt.M
- Neri, I., Jasonni, V. M., Gori, G. F., Blasi, I., and Facchinetti, F. Effect of L-arginine on blood pressure in pregnancy-induced hypertension: a randomized placebo-controlled trial. J Matern.Fetal Neonatal Med. 2006;19(5):277-281.
- Lucotti, P., Setola, E., Monti, L. D., Galluccio, E., Costa, S., Sandoli, E. P., Fermo, I., Rabaiotti, G., Gatti, R., and Piatti, P. Beneficial effects of a long-term oral L-arginine treatment added to a hypocaloric diet and exercise training program in
- Savoye, G., Jemaa, Y., Mosni, G., Savoye-Collet, C., Morcamp, P., Dechelotte, P., Bouin, M., Denis, P., and Ducrotte, P. Effects of intragastric L-arginine administration on proximal stomach tone under basal conditions and after an intragastric diet. Dig PubMed
- Facchinetti, F., Saade, G. R., Neri, I., Pizzi, C., Longo, M., and Volpe, A. L-arginine supplementation in patients with gestational hypertension: a pilot study. Hypertens.Pregnancy. 2007;26(1):121-130. PubMed
- Jovanovic, A., Gerrard, J., and Taylor, R. The second-meal phenomenon in type 2 diabetes. Diabetes Care 2009;32(7):1199-1201. PubMed
- Fontanive P, Saponati G, Iurato A, et al. Effects of L-arginine on the Minnesota Living with Heart Failure Questionnaire quality-of-life score in patients with chronic systolic heart failure. Med.Sci.Monit. 2009;15:CR606-11.
- Doutreleau, S., Rouyer, O., Di, Marco P., Lonsdorfer, E., Richard, R., Piquard, F., and Geny, B. L-arginine supplementation improves exercise capacity after a heart transplant. Am J Clin.Nutr. 2010;91(5):1261-1267. PubMed
- Ast, J., Jablecka, A., Bogdanski, P., Smolarek, I., Krauss, H., and Chmara, E. Evaluation of the antihypertensive effect of L-arginine supplementation in patients with mild hypertension assessed with ambulatory blood pressure monitoring. Med.Sci.Monit. 2
- Saleh, A. I., Abdel Maksoud, S. M., El-Maraghy, S. A., and Gad, M. Z. Protective effect of L-arginine in experimentally induced myocardial ischemia: comparison with aspirin. J Cardiovasc.Pharmacol.Ther 2011;16(1):53-62. PubMed
- Dong, J. Y., Qin, L. Q., Zhang, Z., Zhao, Y., Wang, J., Arigoni, F., and Zhang, W. Effect of oral L-arginine supplementation on blood pressure: a meta-analysis of randomized, double-blind, placebo-controlled trials. Am.Heart J 2011;162(6):959-965. PubMed
- Hertz, P. and Richardson, J. A. Arginine-induced hyperkalemia in renal failure patients. Arch.Intern.Med. 1972;130(5):778-780. DOI
- Bushinsky, D. A. and Gennari, F. J. Life-threatening hyperkalemia induced by arginine. Ann.Intern.Med. 1978;89(5 Pt 1):632-634. PubMed
- Adams, M. R., Forsyth, C. J., Jessup, W., Robinson, J., and Celermajer, D. S. Oral L-arginine inhibits platelet aggregation but does not enhance endothelium-dependent dilation in healthy young men. J Am Coll.Cardiol 1995;26(4):1054-1061. PubMed
- Dell'Omo, G., Catapano, G., Ebel, M., Gazzano, A., Ducci, M., Del, Chicca M., Clerico, A., and Pedrinelli, R. [Pressor, renal and endocrine effects of systemic infusion of L-arginine in hypertensive patients]. Ann.Ital Med.Int. 1995;10(2):107-112.
- Higashi, Y., Oshima, T., Ozono, R., Watanabe, M., Matsuura, H., and Kajiyama, G. Effects of L-arginine infusion on renal hemodynamics in patients with mild essential hypertension. Hypertension 1995;25(4 Pt 2):898-902.
- Bode-Boger, S. M., Boger, R. H., Creutzig, A., Tsikas, D., Gutzki, F. M., Alexander, K., and Frolich, J. C. L-arginine infusion decreases peripheral arterial resistance and inhibits platelet aggregation in healthy subjects. Clin.Sci.(Lond) 1994;87(3):303
- Marfella, R., Acampora, R., Verrazzo, G., Ziccardi, P., De, Rosa N., Giunta, R., and Giugliano, D. Metformin improves hemodynamic and rheological responses to L-arginine in NIDDM patients. Diabetes Care 1996;19(9):934-939. PubMed
- Giugliano, D., Marfella, R., Verrazzo, G., Acampora, R., Coppola, L., Cozzolino, D., and D'Onofrio, F. The vascular effects of L-Arginine in humans. The role of endogenous insulin. J Clin.Invest 2-1-1997;99(3):433-438. PubMed
- Khan, F., Litchfield, S. J., McLaren, M., Veale, D. J., Littleford, R. C., and Belch, J. J. Oral L-arginine supplementation and cutaneous vascular responses in patients with primary Raynaud's phenomenon. Arthritis Rheum. 1997;40(2):352-357.
- Wolf, A., Zalpour, C., Theilmeier, G., Wang, B. Y., Ma, A., Anderson, B., Tsao, P. S., and Cooke, J. P. Dietary L-arginine supplementation normalizes platelet aggregation in hypercholesterolemic humans. J Am Coll.Cardiol 3-1-1997;29(3):479-485. PubMed
- Schellong, S. M., Boger, R. H., Burchert, W., Bode-Boger, S. M., Galland, A., Frolich, J. C., Hundeshagen, H., and Alexander, K. Dose-related effect of intravenous L-arginine on muscular blood flow of the calf in patients with peripheral vascular disease
- Marietta, M., Facchinetti, F., Neri, I., Piccinini, F., Volpe, A., and Torelli, G. L-arginine infusion decreases platelet aggregation through an intraplatelet nitric oxide release. Thromb.Res 10-15-1997;88(2):229-235. PubMed
- Bauer JD, Isenring E, Waterhouse M. The effectiveness of a specialised oral nutrition supplement on outcomes in patients with chronic wounds: a pragmatic randomised study. J Hum Nutr Diet. 2013 Oct;26(5):452-8. PubMed
- Vadillo-Ortega F, Perichart-Perera O, Espino S, et al. Effect of supplementation during pregnancy with L-arginine and antioxidant vitamins in medical food on pre-eclampsia in high risk population: randomised controlled trial. BMJ. 2011 May 19;342:d2901. PubMed
- Camarena Pulido EE, García Benavides L, Panduro Barón JG, et al. Efficacy of L-arginine for preventing preeclampsia in high-risk pregnancies: A double-blind, randomized, clinical trial. Hypertens Pregnancy. 2016;35(2):217-25. PubMed
- Yokota T, Hamauchi S, Yoshida Y, et al. A phase II study of HMB/Arg/Gln against oral mucositis induced by chemoradiotherapy for patients with head and neck cancer. Support Care Cancer. 2018;26(9):3241-3248. PubMed
- Binet Q, Dufour I, Agneessens E, et al. The second case of a young man with L-arginine-induced acute pancreatitis. Clin J Gastroenterol. 2018;11(5):424-427. PubMed
- El Taieb M, Hegazy E, Ibrahim A. Daily oral l-arginine plus tadalafil in diabetic patients with erectile dysfunction: A double-blinded, randomized, controlled clinical trial. J Sex Med. 2019;16(9):1390-1397.
- Gallo L, Pecoraro S, Sarnacchiaro P, Silvani M, Antonini G. The daily therapy with L-arginine 2,500 mg and tadalafil 5 mg in combination and in monotherapy for the treatment of erectile dysfunction: A prospective, randomized multicentre study. Sex Med. 20 PubMed
- de la Parra PR, González-Cruz MÁ, Ferreiro-Marin A, Casaubón-Garcín PR. L-arginine-induced esophagitis, report of six cases. Bol Med Hosp Infant Mex. 2020;77(1):38-41. PubMed
- El-Wakeel LM, Fouad FA, Saleem MD, Saber-Khalaf M. Efficacy and tolerability of sildenafil/l-arginine combination relative to sildenafil alone in patients with organic erectile dysfunction. Andrology. 2020;8(1):143-147.
- Abu El-Hamd M, Hegazy EM. Comparison of the clinical efficacy of daily use of L-arginine, tadalafil and combined L-arginine with tadalafil in the treatment of elderly patients with erectile dysfunction. Andrologia. 2020;52(7):e13640. PubMed
- Liao SY, Showalter MR, Linderholm AL, et al. l-Arginine supplementation in severe asthma. JCI Insight. 2020;5(13):e137777. PubMed
- Yousefi Rad E, Nazarian B, Saboori S, Falahi E, Hekmatdoost A. Effects of l-arginine supplementation on glycemic profile: Evidence from a systematic review and meta-analysis of clinical trials. J Integr Med. 2020;18(4):284-291. PubMed
- Xu Z, Liu C, Liu S, Zhou Z. Comparison of efficacy and safety of daily oral L-arginine and PDE5Is alone or combination in treating erectile dysfunction: A systematic review and meta-analysis of randomised controlled trials. Andrologia. 2021:e14007. PubMed
- Goto E. Effects of prenatal oral L-arginine on birth outcomes: a meta-analysis. Sci Rep 2021;11(1):22748. PubMed
- Monari F, Menichini D, Pignatti L, Basile L, Facchinetti F, Neri I. Effect of L-arginine supplementation in pregnant women with chronic hypertension and previous placenta vascular disorders receiving Aspirin prophylaxis: a randomized control trial. Minerv PubMed
- Li H, Liu Q, Zou Z, et al. L-arginine supplementation to mitigate cardiovascular effects of walking outside in the context of traffic-related air pollution in participants with elevated blood pressure: A randomized, double-blind, placebo-controlled trial. PubMed
- Shiraseb F, Asbaghi O, Bagheri R, Wong A, Figueroa A, Mirzaei K. The Effect of L-arginine Supplementation On Blood Pressure in Adults: A Systematic Review and Dose-response Meta-analysis of Randomized Clinical Trials. Adv Nutr 2021. PubMed
L-citrulline 8 references
- Cheng JW, Balwin SN. L-arginine in the management of cardiovascular diseases. Ann Pharmacother 2001;35:755-64. PubMed
- Schwedhelm E, Maas R, Freese R, et al. Pharmacokinetic and pharmacodynamic properties of oral L-citrulline and L-arginine: impact on nitric oxide metabolism. Br J Clin Pharmacol 2008;65:51-9. PubMed
- Romero MJ, Platt DH, Caldwell RB, Caldwell RW. Therapeutic use of citrulline in cardiovascular disease. Cardiovasc Drug Rev 2006;24:275-90. PubMed
- Balderas-Munoz K, Castillo-Martínez L, Orea-Tejeda A, et al. Improvement of ventricular function in systolic heart failure patients with oral L-citrulline supplementation. Cardiol J 2012;19:612-7. PubMed
- Sharif Kashani B, Tahmaseb Pour P, Malekmohammad M, et al. Oral l-citrulline malate in patients with idiopathic pulmonary arterial hypertension and Eisenmenger Syndrome: a clinical trial. J Cardiol 2014;64:231-5. PubMed
- Pérez-Guisado J, Jakeman PM. Citrulline malate enhances athletic anaerobic performance and relieves muscle soreness. J Strength Cond Res 2010;24:1215-22. PubMed
- Mirenayat MS, Moradi S, Mohammadi H, Rouhani MH. Effect of L-citrulline supplementation on blood pressure: a systematic review and meta-analysis of clinical trials. Curr Hypertens Rep. 2018;20(11):98. PubMed
- Xu Z, Liu C, Liu S, Zhou Z. Comparison of efficacy and safety of daily oral L-arginine and PDE5Is alone or combination in treating erectile dysfunction: A systematic review and meta-analysis of randomised controlled trials. Andrologia. 2021:e14007. PubMed
Vitamin D 26 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Tatro DS, ed. Drug Interactions Facts. Facts and Comparisons Inc., St. Louis, MO. 1999.
- Koutkia P, Chen TC, Holick MF. Vitamin D intoxication associated with an over-the-counter supplement. N Engl J Med 2001;345:66-7. PubMed
- Bar-Or D, Yoel G. Calcium and calciferol antagonize effect of verapamil in atrial fibrillation. Br Med J 1981;282:1585-6.
- Demontis R, Leflon A, Fournier A, et al. 1 alpha(OH) vitamin D3 increases plasma aluminum in hemodialyzed patients taking AI(OH)3. Clin Nephrol 1986;26:146-9.
- Crowe M, Wollner L, Griffiths RA. Hypercalcemia following vitamin D and thiazide therapy in the elderly. Practitioner 1984;228:312-3.
- Parfitt AM. Thiazide-induced hypercalcemia in vitamin D-treated hypoparathyroidism. Ann Intern Med 1972;77:557-63. PubMed
- Thiazide diuretics and the risk of osteoporosis. Pharmacist's Letter/Prescriber's Letter 2003;19(11):191105.
- Moon J. The role of vitamin D in toxic metal absorption. J Am Coll Nutr 1994;13:559-64.
- Demontis R, Reissi D, Noel C, et al. Indirect clinical evidence that 1alphaOH vitamin D<SUB>3</SUB> increases the intestinal absorption of aluminum. Clin Nephrol 1989;31:123-7.
- Adler AJ, Berlyne GM. Duodenal aluminum absorption in the rat: effect of vitamin D. Am J Physiol 1985;249:G209-13. PubMed
- Schwartz JB. Effects of vitamin D supplementation in atorvastatin-treated patients: A new drug interaction with an unexpected consequence. Clin Pharmacol Ther 2009;85:198-203. PubMed
- Dietary reference intakes for calcium and vitamin D. Institute of Medicine, November 30, 2010. Available at: http://www.iom.edu/~/media/Files/Report%20Files/2010/Dietary-Reference-Intakes-for-Calcium-and-Vitamin-D/Vitamin%20D%20and%20Calcium%202010%20Repo
- Cox KA, Dunn MA. Aluminum toxicity alters the regulation of calbindin-D28k protein and mRNA expression in chick intestine. J Nutr 2001;131:2007-13. PubMed
- Escribano, J., Balaguer, A., Pagone, F., Feliu, A., and Roque, I. Figuls. Pharmacological interventions for preventing complications in idiopathic hypercalciuria. Cochrane.Database.Syst.Rev. 2009;(1):CD004754. PubMed
- Carlton, S., Clopton, D., and Cappuzzo, K. A. Vitamin D deficiency: appropriate replenishment therapies and the effects of vitamin D toxicity. Consult Pharm 2010;25(3):171-177. PubMed
- Wang, H., Xia, N., Yang, Y., and Peng, D. Q. Influence of vitamin D supplementation on plasma lipid profiles: a meta-analysis of randomized controlled trials. Lipids Health Dis. 2012;11:42. PubMed
- Turner AN, Carr Reese P, Fields KS, Anderson J, Ervin M, Davis JA, Fichorova RN, Roberts MW, Klebanoff MA, Jackson RD. A blinded, randomized controlled trial of high-dose vitamin D supplementation to reduce recurrence of bacterial vaginosis. Am J Obstet G PubMed
- Weiner M, Epstein FH. Signs and symptoms of electrolyte disorders. Yale J Biol Med. 1970;43(2):76-109.
- Lappe J, Watson P, Travers-Gustafson D, Recker R, Garland C, Gorham E, Baggerly K, McDonnell SL. Effect of Vitamin D and Calcium Supplementation on Cancer Incidence in Older Women: A Randomized Clinical Trial. JAMA. 2017 Mar 28;317(12):1234-1243. PubMed
- Roth DE, Leung M, Mesfin E, Qamar H, Watterworth J, Papp E. Vitamin D supplementation during pregnancy: state of the evidence from a systematic review of randomised trials. BMJ. 2017;359:j5237. PubMed
- Murai IH, Fernandes AL, Sales LP, et al. Effect of a single high dose of vitamin D3 on hospital length of stay in patients with moderate to severe COVID-19: A randomized clinical trial. JAMA. 2021.
- Wang Z, Schuetz EG, Xu Y, Thummel KE. Interplay between vitamin D and the drug metabolizing enzyme CYP3A4. J Steroid Biochem Mol Biol 2013;136:54-8. PubMed
- Doyle D, Browne U, Brickley A, Murphy D. Vitamin D-induced hypercalcaemia and acute kidney injury in sarcoidosis. BMJ Case Rep 2023;16(1):e250580. PubMed
- Williamson A, Martineau AR, Sheikh A, Jolliffe D, Griffiths CJ. Vitamin D for the management of asthma. Cochrane Database Syst Rev 2023;2(2):CD011511. PubMed
- Kinesya E, Santoso D, Gde Arya N, et al. Vitamin D as adjuvant therapy for diabetic foot ulcers: Systematic review and meta-analysis approach. Clin Nutr ESPEN 2023;54:137-143. PubMed
Zinc 88 references
- Barceloux DG. Zinc. J Toxicol Clin Toxicol 1999;37:279-92.
- Eby GA, Davis DR, Halcomb WW. Reduction in duration of common colds by zinc gluconate lozenges in a double-blind study. Antimicrob Agents Chemother 1984;25:20-4. DOI
- Smith DS, Helzner EC, Nuttall CE Jr, et al. Failure of zinc gluconate in treatment of acute upper respiratory tract infections. Antimicrob Agents Chemother 1989;33:646-8. PubMed
- Blondeau JM. Expanded activity and utility of the new fluoroquinolones: a review. Clin Ther 1999;21:3-40. PubMed
- Reyes AJ, Olhaberry JV, Leary WP, et al. Urinary zinc excretion, diuretics, zinc deficiency and some side-effects of diuretics. S Afr Med J 1983;64:936-41.
- Kugelmas M. Preliminary observation: oral zinc sulfate replacement is effective in treating muscle cramps in cirrhotic patients. J Am Coll Nutr 2000;19:13-5. PubMed
- Hebel SK, ed. Drug Facts and Comparisons. 52nd ed. St. Louis: Facts and Comparisons, 1998.
- Chan S, Gerson B, Subramaniam S. The role of copper, molybdenum, selenium, and zinc in nutrition and health. Clin Lab Med 1998;18:673-85. DOI
- Brewer GJ, Yuzbasiyan-Gurkan V, Johnson V, et al. Treatment of Wilson's disease with zinc: XI. Interaction with other anticopper agents. J Am Coll Nutr 1993;12:26-30. PubMed
- Fosmire GJ. Zinc toxicity. Am J Clin Nutr 1990;51:225-7.
- Lomaestro BM, Bailie GR. Absorption interactions with fluoroquinolones. 1995 update. Drug Saf 1995;12:314-33. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Seelig MS. Auto-immune complications of D-penicillamine - A possible result of zinc and magnesium depletion and of pyridoxine inactivation. J Am Coll Nutr 1982;1:207-14. PubMed
- Neuvonen PJ. Interactions with the absorption of tetracyclines. Drugs 1976;11:45-54.. PubMed
- Hirt M, Nobel S, Barron E. Zinc nasal gel for the treatment of common cold symptoms: A double-blind, placebo-controlled trial. Ear Nose Throat J 2000;79:778-82.. DOI
- Simkin PA. Oral zinc sulphate in rheumatoid arthritis. Lancet 1976;2:539-42. PubMed
- Wray D. A double-blind trial of systemic zinc sulfate in recurrent aphthous stomatitis. Oral Surg Oral Med Oral Pathol 1982;53:469-72. PubMed
- Douglas RM, Miles HB, Moore BW, et al. Failure of effervescent zinc acetate lozenges to alter the course of upper respiratory tract infections in Australian adults. Antimicrob Agents Chemother 1987;31:1263-5. PubMed
- Lagiou P, Wuu J, Trichopoulou A, et al. Diet and benign prostatic hyperplasia: a study in Greece. Urology 1999;54:284-90. PubMed
- Ewing CI, Gibbs AC, Ashcroft C, David TJ. Failure of oral zinc supplementation in atopic eczema. Eur J Clin Nutr 1991;45:507-10.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Age-Related Eye Disease Study Research Group. A randomized, placebo-controlled, clinical trial of high-dose supplementation with vitamins C and E, beta carotene, and zinc for age-related macular degeneration and vision loss. AREDS report no. 8. Arch Oph
- Greenberg JE, Lynn M, Kirsner RS, et al. Mucocutaneous pigmented macule as a result of zinc deposition. J Cutan Pathol 2002;29:613-5. PubMed
- Godfrey HR, Godfrey NJ, Godfrey JC, Riley D. A randomized clinical trial on the treatment of oral herpes with topical zinc oxide/glycine. Altern Ther Health Med 2001;7:49-56.
- Turner RB. Ineffectiveness of intranasal zinc gluconate for prevention of experimental rhinovirus colds. Clin Infect Dis 2001;33:1865-70. PubMed
- Belongia EA, Berg R, Liu K. A randomized trial of zinc nasal spray for the treatment of upper respiratory illness in adults. Am J Med 2001;111:103-8. PubMed
- Mossad SB. Effect of zincum gluconicum nasal gel on the duration and symptom severity of the common cold in otherwise healthy adults. QJM 2003;96:35-43. DOI
- Leitzmann MF, Stampfer MJ, Wu K, et al. Zinc supplement use and risk of prostate cancer. J Natl Cancer Inst 2003;95:1004-7.. PubMed
- Jafek BW, Linschoten M, Murrow BW. Zicam Induced Anosmia. American Rhinologic Society 49th Annual Fall Scientific Meeting abstract. Orlando, Florida. September 20, 2003. http://app.american-rhinologic.org/programs/2003ARSFallProgram071503.pdf (Accessed 24
- Uebayashi H, Hatanaka T, Kanemura F, Tonosaki K. Acute anosmia in the mouse: behavioral discrimination among the four basic taste substances. Physiol Behav 2001;72:291-6.. PubMed
- Barrett S. Zicam Marketers Sued. United States District Court Western District of Michigan Southern Division, Filed October 14, 2003, Case No. 4:03CV0146.
- Bilici M, Yildirim F, Kandil S, et al. Double-blind, placebo-controlled study of zinc sulfate in the treatment of attention deficit hyperactivity disorder. Prog Neuropsychopharmacol Biol Psychiatry 2004;28:181-90.. PubMed
- Polk RE, Healy DP, Sahai J, et al. Effect of ferrous sulfate and multivitamins with zinc on absorption of ciprofloxacin in normal volunteers. Antimicrob Agents Chemother 1989;33:1841-4. PubMed
- Mery C, Delrieu F, Ghozlan R, et al. Controlled trial of D-penicillamine in rheumatoid arthritis. Dose effect and the role of zinc. Scand J Rheumatol 1976;5:241-7. PubMed
- Penttila O, Hurme H, Neuvonen PJ. Effect of zinc sulfate on the absorption of tetracycline and doxycycline in man. Eur J Clin Pharmacol 1975;9:131-4.
- Kondo Y, Yamagata K, Satoh M, et al. Optimal administration schedule of cisplatin for bladder tumor with minimal induction of metallothionein. J Urol 2003;170:2467-70. PubMed
- Doz F, Berens ME, Deschepper CF, et al. Experimental basis for increasing the therapeutic index of cis-diamminedicarboxylatocyclobutaneplatinum(II) in brain tumor therapy by a high-zinc diet. Cancer Chemother Pharmacol 1992;29:219-26.
- Wester PO. Urinary zinc excretion during treatment with different diuretics. Acta Med Scand 1980;208:209-12. PubMed
- Golik A, Modai D, Weissgarten J, et al. Hydrochlorothiazide-amiloride causes excessive urinary zinc excretion. Clin Pharmacol Ther 1987;42:42-4. PubMed
- Leary WP, Reyes AJ, Van der Byl K. Urinary magnesium and zinc excretion after two different single doses of amiloride in healthy adults. Curr Ther Res 1983;34:205-16.
- McBride K, Slotnick B, Margolis FL. Does intranasal application of zinc sulfate produce anosmia in the mouse? An olfactometric and anatomical study. Chem Senses 2003;28:659-70. PubMed
- Burd GD. Morphological study of the effects of intranasal zinc sulfate irrigation on the mouse olfactory epithelium and olfactory bulb. Microsc Res Tech 1993;24:195-213. PubMed
- Ducray A, Bondier JR, Michel G, et al. Recovery following peripheral destruction of olfactory neurons in young and adult mice. Eur J Neurosci 2002;15:1907-17. PubMed
- Mayer AD, Rosenblatt JS. Peripheral olfactory deafferentation of the primary olfactory system in rats using ZnSO4 nasal spray with special reference to maternal behavior. Physiol Behav 1993;53:587-92. PubMed
- DeCook CA, Hirsch AR. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Tisdall FF, Brown A, Defries RD. Persistent anosmia following zinc sulfate nasal spraying. JPed 1938;18:60-2. DOI
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Public Health Advisory. Loss of sense of smell with intranasal cold remedies containing zinc. U.S. Food and Drug Administration, June 16, 2009. Available at: http://www.fda.gov/Drugs/DrugSafety/PublicHealthAdvisories/ucm166059.htm (Accessed 16 June 2009)
- Dooren JC. FDA warns against use of Zicam. The Wall Street Journal, June 16, 2009. Available at: http://online.wsj.com/article/SB124516778692319231.html#mod=djemHL?mg=com-wsj (Accessed 16 June 2009).
- Alexander TH, Davidson TM. Intranasal zinc and anosmia: the zinc-induced anosmia syndrome. Laryngoscope 2006;116:217-20.
- Health Canada / GlaxoSmithKline Consumer Healthcare. Association of long-term, excessive use of zinc-containing Poli-Grip products with myeloneuropathy and blood dyscrasias. February 18, 2010. Available at: http://hc-sc.gc.ca/dhp-mps/alt_formats/pdf/medef
- GlaxoSmithKline Consumer Advisory. GlaxoSmithKline (GSK) warns about a potential health risk associated with long-term, excessive use of GSK's zinc-containing denture adhesives Super Polygrip Original, Ultra Fresh and Extra Care. February 18, 2010. Availa
- Science M, Johnstone J, Roth DE, et al. Zinc for the treatment of the common cold: a systematic review and meta-analysis of randomized controlled trials. CMAJ 2012;184:E551-61. PubMed
- Castilla-Higuero, L., Romero-Gomez, M., Suarez, E., and Castro, M. Acute hepatitis after starting zinc therapy in a patient with presymptomatic Wilson's disease. Hepatology 2000;32(4 Pt 1):877. PubMed
- Sharquie, K. E., Najim, R. A., Farjou, I. B., and Al Timimi, D. J. Oral zinc sulphate in the treatment of acute cutaneous leishmaniasis. Clin.Exp.Dermatol. 2001;26(1):21-26. PubMed
- Dreno, B., Moyse, D., Alirezai, M., Amblard, P., Auffret, N., Beylot, C., Bodokh, I., Chivot, M., Daniel, F., Humbert, P., Meynadier, J., and Poli, F. Multicenter randomized comparative double-blind controlled clinical trial of the safety and efficacy of
- Moore, R. Bleeding gastric erosion after oral zinc sulphate. Br.Med J 3-25-1978;1(6115):754. PubMed
- Jafek, B. W., Linschoten, M. R., and Murrow, B. W. Anosmia after intranasal zinc gluconate use. Am J Rhinol. 2004;18(3):137-141. DOI
- Simonart, T. and de, Maertelaer, V. Systemic treatments for cutaneous warts: a systematic review. J Dermatolog.Treat. 2012;23(1):72-77. PubMed
- Cochran, R. J., Tucker, S. B., and Flannigan, S. A. Topical zinc therapy for acne vulgaris. Int.J Dermatol. 1985;24(3):188-190. DOI
- Morgan, A. A. Bleeding gastric erosion after oral zinc sulphate. Br.Med.J. 5-13-1978;1(6122):1283-1284. PubMed
- Murphy, J. V. Intoxication following ingestion of elemental zinc. JAMA 6-22-1970;212(12):2119-2120.
- Lang, C. J., Rabas-Kolominsky, P., Engelhardt, A., Kobras, G., and Konig, H. J. Fatal deterioration of Wilson's disease after institution of oral zinc therapy. Arch Neurol. 1993;50(10):1007-1008. PubMed
- Fjellner, B. Drug-induced lupus erythematosus aggravated by oral zinc therapy. Acta Derm.Venereol. 1979;59(4):368-370. DOI
- Varas Lorenzo, M. J. Zinc acexamate and ranitidine in the short- and mid-term management of gastroduodenal ulcers. Curr Ther Res 21986;39:19-29.
- Bosch, F. and Jimenez, E. Post-marketing surveillance of zinc acexamate in peptic ulcer treatment. Clin Trials J 1990;27:301-312.
- DeCook, C. A. and Hirsch, A. R. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Crown LA, May JA. Zinc toxicity: denture adhesives, bone marrow failure and polyneuropathy. Tenn Med. 2012 Feb;105(2):39-40, 42.
- Dadamio J, Van Tournout M, Teughels W, Dekeyser C, Coucke W, Quirynen M. Efficacy of different mouthrinse formulations in reducing oral malodour: a randomized clinical trial. J Clin Periodontol. 2013 May;40(5):505-13. PubMed
- Moyle G, Else L, Jackson A, Back D, Yapa MH, Seymour N, Ringner-Nackter L, Karolia Z, Gazzard B, Boffito M. Coadministration of atazanavir-ritonavir and zinc sulfate: impact on hyperbilirubinemia and pharmacokinetics. Antimicrob Agents Chemother. 2013 Aug PubMed
- Zittel S, Ufer F, Gerloff C, Münchau A, Rosenkranz M. Severe myelopathy after denture cream use--is copper deficiency or excess zinc the cause? Clin Neurol Neurosurg. 2014 Jun;121:17-8. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Guidelines for the Use of Antiretroviral Agents in HIV-1-Infected Adults and Adolescents: Drug Interactions between Integrase Inhibitors and Other Drugs. AIDSinfo. July 14, 2016. Available at: https://aidsinfo.nih.gov/guidelines/html/1/adult-and-adolescen
- Ding Y, Jia YY, Li F, et al. The effect of staggered administration of zinc sulfate on the pharmacokinetics of oral cephalexin. Br J Clin Pharmacol. 2012 Mar;73(3):422-7. PubMed
- Fallah R, Sabbaghzadegan S, Karbasi SA, Binesh F. Efficacy of zinc sulfate supplement on febrile seizure recurrence prevention in children with normal serum zinc level: A randomised clinical trial. Nutrition. 2015;31(11-12):1358-61. PubMed
- Lazzerini M, Wanzira H. Oral zinc for treating diarrhoea in children. Cochrane Database Syst Rev. 2016;12:CD005436. PubMed
- Mahmoud AM, Al-Alem U, Dabbous F, et al. Zinc intake and risk of prostate cancer: Case-control study and meta-analysis. PLoS One. 2016;11(11):e0165956. PubMed
- Nagraj SK, George RP, Shetty N, Levenson D, Ferraiolo DM, Shrestha A. Interventions for managing taste disturbances. Cochrane Database Syst Rev. 2017 Dec 20;12(12):CD010470. PubMed
- Yee BE, Richards P, Sui JY, Marsch AF. Serum zinc levels and efficacy of zinc treatment in acne vulgaris: A systematic review and meta-analysis. Dermatol Ther. 2020:e14252. PubMed
- Janyajirawong R, Vilaichone RK, Sethasine S. Efficacy of zinc supplement in minimal hepatic encephalopathy: A prospective, randomized controlled study (Zinc-MHE Trial). Asian Pac J Cancer Prev 2021;22(9):2879-2887. PubMed
- Nakano M, Nakamura Y, Miyazaki A, Takahashi J. Zinc pharmacotherapy for elderly osteoporotic patients with zinc deficiency in a clinical setting. Nutrients 2021;13(6):1814. PubMed
- Tolino E, Skroza N, Mambrin A, et al. An open-label study comparing oral zinc to lymecycline in the treatment of acne vulgaris. J Clin Aesthet Dermatol 2021;14(5):56-58.
- Hunter J, Arentz S, Goldenberg J, et al. Zinc for the prevention or treatment of acute viral respiratory tract infections in adults: a rapid systematic review and meta-analysis of randomised controlled trials. BMJ Open. 2021;11(11):e047474. PubMed
- Yamazaki K, Kageyama H, Fujiyama T, Ito T, Urano S, Honda T. A case of systemic contact dermatitis due to zinc supplements. Int J Dermatol 2022. PubMed
- Magham K, Han J, Eilbert W, Bunney EB. Severe copper deficiency anemia caused by zinc supplement use. Am J Emerg Med 2023;72:222. PubMed
- Sivakumar RR, Chinnaiah Govindareddy D, Sahoo J, Bobby Z, Chinnakali P. Effect of daily zinc supplementation for 12 weeks on serum thyroid auto-antibody levels in children and adolescents with autoimmune thyroiditis - a randomized controlled trial. J Pedi PubMed
- AlDhasee O, AlMalki H, AlKharashi N, AlJeraisy N, Al Deeb M. Acute zinc sulfate overdose: clinical presentation and management. BMJ Case Rep 2025;18(1):e263899. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Niacin 66 references
- Garg R, Malinow MR, Pettinger M, et al. Niacin treatment increases plasma homocysteine levels. Am Heart J 1999;138:1082-7.
- Anon. Inositol hexaniacinate. Altern Med Rev 1998;3:222-3.
- Knodel LC, Talbert RL. Adverse effects of hypolipidaemic drugs. Med Toxicol 1987;2:10-32. PubMed
- Guyton JR, Blazing MA, Hagar J, et al. Extended-release niacin vs gemfibrozil for the treatment of low levels of high-density lipoprotein cholesterol. Niaspan-Gemfibrozil Study Group. Arch Intern Med 2000;160:1177-84. PubMed
- Gibbons LW, Gonzalez V, Gordon N, Grundy S. The prevalence of side effects with regular and sustained-release nicotinic acid. Am J Med 1995;99:378-85. PubMed
- Whelan AM, Price SO, Fowler SF, Hainer BL. The effect of aspirin on niacin-induced cutaneous reactions. J Fam Pract 1992;34:165-8.
- Jungnickel PW, Maloley PA, Vander Tuin EL, et al. Effect of two aspirin pretreatment regimens on niacin-induced cutaneous reactions. J Gen Intern Med 1997;12:591-6. PubMed
- Capuzzi DM, Guyton JR, Morgan JM, et al. Efficacy and safety of an extended-release niacin (Niaspan): a long-term study. Am J Cardiol 1998;82:74-81;disc. 85U-6U. PubMed
- Gray DR, Morgan T, Chretien SD, Kashyap ML. Efficacy and safety of controlled-release niacin in dyslipoproteinemic veterans. Ann Intern Med 1994;121:252-8. PubMed
- McKenney JM, Proctor JD, Harris S, Chinchili VM. A comparison of the efficacy and toxic effects of sustained- vs immediate-release niacin in hypercholesterolemic patients. JAMA 1994;271:672-7. DOI
- Knopp RH, Alagona P, Davidson M, et al. Equivalent efficacy of a time-release form of niacin (Niaspan) given once-a-night versus plain niacin in the management of hyperlipidemia. Metabolism 1998;47:1097-104. PubMed
- Knopp RH. Clinical profiles of plain versus sustained-release niacin (Niaspan) and the physiologic rationale for nighttime dosing. Am J Cardiol 1998;82:24U-28U;discussion 39U-41U. PubMed
- Garg A, Grundy SM. Nicotinic acid as therapy for dyslipidemia in non-insulin-dependent diabetes mellitus. JAMA 1990;264:723-6. DOI
- Leighton RF, Gordon NF, Small GS, et al. Dental and gingival pain as side effects of niacin therapy. Chest 1998;114:1472-4. PubMed
- American Society of Health-System Pharmacists. ASHP Therapeutic Position Statement on the safe use of niacin in the management of dyslipidemias. Am J Health Syst Pharm 1997;54:2815-9. DOI
- Vega GL, Grundy SM. Lipoprotein responses to treatment with lovastatin, gemfibrozil, and nicotinic acid in normolipidemic patients with hypoalphalipoproteinemia. Arch Intern Med 1994;154:73-82. DOI
- Guyton JR, Goldberg AC, Kreisberg RA, et al. Effectiveness of once-nightly dosing of extended-release niacin alone and in combination for hypercholesterolemia. Am J Cardiol 1998;82:737-43.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Bays HE, Dujovne CA. Drug interactions of lipid-altering drugs. Drug Saf 1998;19:355-71. PubMed
- Rader JI, Calvert RJ, Hathcock JN. Hepatic toxicity of unmodified and time-release preparations of niacin. Am J Med 1992;92:77-81. PubMed
- Kahn SE, Beard JC, Schwartz MW, et al. Increased B-cell secretory capacity as mechanism for islet adaptation to nicotinic acid-induced insulin resistance. Diabetes 1989;38:562-8.
- Schwartz ML. Severe reversible hyperglycemia as a consequence of niacin therapy. Arch Int Med 1993;153:2050-2. DOI
- Raising HDL and Niacin Use. Pharmacist's Letter/Prescriber's Letter 2004;20(5):200504.
- McKenney J. New perspectives on the use of niacin in the treatment of lipid disorders. Arch Intern Med 2004;164:697-705. PubMed
- Reaven P, Witztum JL. Lovastatin, nicotinic acid and rhabdomyolysis (letter). Ann Int Med 1988;109:597-8. PubMed
- Ito MK. Advances in the understanding and management of dyslipidemia: using niacin-based therapies. Am J Health-Syst Pharm 2003;60(suppl 2):s15-21. PubMed
- Schwab RA, Bachhuber BH. Delirium and lactic acidosis caused by ethanol and niacin coingestion. Am J Emerg Med 1991;9:363-5. PubMed
- Product information: Niaspan. Kos Pharmaceuticals. Cranbury, NJ. 2005. Available at www.niaspan.com/professional/content/pdfs/productinfo.pdf. (Accessed 3 March 2006).
- Ding RW, Kolbe K, Merz B, et al. Pharmacokinetics of nicotinic acid-salicylic acid interaction. Clin Pharmacol Ther 1989;46:642-7. PubMed
- NIH News. NIH stops clinical trial on combination cholesterol treatment. May 26, 2011. http://www.nih.gov/news/health/may2011/nhlbi-26.htm. (Accessed 3 June 2011).
- Dearing BD, Lavie CJ, Lohmann TP, Genton E. Niacin-induced clotting factor synthesis deficiency with coagulopathy. Arch Intern Med. 1992;152(4):861-3. DOI
- O'Brien T, Silverberg JD, Nguyen TT. Nicotinic acid-induced toxicity associated with cytopenia and decreased levels of thyroxine-binding globulin. Mayo Clin Proc. 1992;67(5):465-8. PubMed
- Gadegbeku CA, Dhandayuthapani A, Shrayyef MZ, Egan BM. Hemodynamic effects of nicotinic acid infusion in normotensive and hypertensive subjects. Am J Hypertens. 2003;16(1):67-71. PubMed
- Garnett WR. Interactions with hydroxymethylglutaryl-coenzyme A reductase inhibitors. Am J Health Syst Pharm. 1995;52(15):1639-45. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Dunn RT, Ford MA, Rindone JP, Kwiecinski FA. Low-Dose Aspirin and Ibuprofen Reduce the Cutaneous Reactions Following Niacin Administration. Am J Ther. 1995;2(7):478-480. PubMed
- Cashin-Hemphill L, Spencer CA, Nicoloff JT, et al. Alterations in serum thyroid hormonal indices with colestipol-niacin therapy. Ann Intern Med. 1987;107(3):324-9. PubMed
- Drinka PJ. Alterations in thyroid and hepatic function tests associated with preparations of sustained-release niacin. Mayo Clin Proc. 1992;67(12):1206. PubMed
- Shakir KM, Kroll S, Aprill BS, Drake AJ 3rd, Eisold JF. Nicotinic acid decreases serum thyroid hormone levels while maintaining a euthyroid state. Mayo Clin Proc. 1995;70(6):556-8. PubMed
- Etchason JA, Miller TD, Squires RW, et al. Niacin-induced hepatitis: a potential side effect with low-dose time-release niacin. Mayo Clin Proc. 1991;66(1):23-8. PubMed
- Henkin Y, Johnson KC, Segrest JP. Rechallenge with crystalline niacin after drug-induced hepatitis from sustained-release niacin. JAMA. 1990;264(2):241-3. DOI
- Henkin Y, Oberman A, Hurst DC, Segrest JP. Niacin revisited: clinical observations on an important but underutilized drug. Am J Med. 1991;91(3):239-46. PubMed
- Brown BG, Bardsley J, Poulin D, et al. Moderate dose, three-drug therapy with niacin, lovastatin, and colestipol to reduce low-density lipoprotein cholesterol <100 mg/dl in patients with hyperlipidemia and coronary artery disease. Am J Cardiol. 1997;80(2)
- Goldberg A, Alagona P Jr, Capuzzi DM, et al. Multiple-dose efficacy and safety of an extended-release form of niacin in the management of hyperlipidemia. Am J Cardiol. 2000;85(9):1100-5. PubMed
- Aronov DM, Keenan JM, Akhmedzhanov NM, et al. Clinical trial of wax-matrix sustained-release niacin in a Russian population with hypercholesterolemia. Arch Fam Med. 1996;5(10):567-75. PubMed
- Morgan JM, Capuzzi DM, Guyton JR, et al. Treatment Effect of Niaspan, a Controlled-release Niacin, in Patients With Hypercholesterolemia: A Placebo-controlled Trial. J Cardiovasc Pharmacol Ther. 1996;1(3):195-202. PubMed
- Andersson RG, Aberg G, Brattsand R, Ericsson E, Lundholm L. Studies on the mechanism of flush induced by nicotinic acid. Acta Pharmacol Toxicol (Copenh). 1977 Jul;41(1):1-10. PubMed
- Brown WV. Niacin for lipid disorders. Indications, effectiveness, and safety. Postgrad Med. 1995 Aug;98(2):185-9, 192-3. PubMed
- O'REILLY PO, CALLBECK MJ, HOFFER A. Sustained-release nicotinic acid (nicospan); effect on (1) cholesterol levels and (2) leukocytes. Can Med Assoc J. 1959;80(5):359-62.
- Gharavi AG, Diamond JA, Smith DA, Phillips RA. Niacin-induced myopathy. Am J Cardiol. 1994;74(8):841-2. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Fraunfelder FW, Fraunfelder FT, Illingworth DR. Adverse ocular effects associated with niacin therapy. Br J Ophthalmol 1995;79:54-56. PubMed
- Ali EH, McJunkin B, Jubelirer S, Hood W. Niacin induced coagulopathy as a manifestation of occult liver injury. W V Med J. 2013 Jan-Feb;109(1):12-4
- Aramwit P, Srisawadwong R, Supasyndh O. Effectiveness and safety of extended-release nicotinic acid for reducing serum phosphorus in hemodialysis patients. J Nephrol. 2012 May-Jun;25(3):354-62. PubMed
- Bassan M. A case for immediate-release niacin. Heart Lung. 2012 Jan-Feb;41(1):95-8. PubMed
- Davidson MH, Rooney M, Pollock E, Drucker J, Choy Y. Effect of colesevelam and niacin on low-density lipoprotein cholesterol and glycemic control in subjects with dyslipidemia and impaired fasting glucose. J Clin Lipidol. 2013 Sep-Oct;7(5):423-32. PubMed
- Guyton JR, Fazio S, Adewale AJ, Jensen E, Tomassini JE, Shah A, Tershakovec AM. Effect of extended-release niacin on new-onset diabetes among hyperlipidemic patients treated with ezetimibe/simvastatin in a randomized controlled trial. Diabetes Care. 2012 PubMed
- Loebl T, Raskin S. A novel case report: acute manic psychotic episode after treatment with niacin. J Neuropsychiatry Clin Neurosci. 2013 Fall;25(4):E14. PubMed
- Teo KK, Goldstein LB, Chaitman BR, Grant S, Weintraub WS, Anderson DC, Sila CA, Cruz-Flores S, Padley RJ, Kostuk WJ, Boden WE; AIM-HIGH Investigators. Extended-release niacin therapy and risk of ischemic stroke in patients with cardiovascular disease: the
- Goldie C, Taylor AJ, Nguyen P, McCoy C, Zhao XQ, Preiss D. Niacin therapy and the risk of new-onset diabetes: a meta-analysis of randomized controlled trials. Heart. 2016 Feb;102(3):198-203.
- Schandelmaier S, Briel M, Saccilotto R, Olu KK, Arpagaus A, Hemkens LG, Nordmann AJ. Niacin for primary and secondary prevention of cardiovascular events. Cochrane Database Syst Rev. 2017 Jun 14;6:CD009744. PubMed
- Jenkins DJA, Spence JD, Giovannucci EL, et al. Supplemental vitamins and minerals for CVD prevention and treatment. J Am Coll Cardiol 2018;71(22):2570-84. PubMed
- Song S, Lee CJ, Oh J, Park S, Kang SM, Lee SH. Effect of Niacin on Carotid Atherosclerosis in Patients at Low-Density Lipoprotein-Cholesterol Goal but High Lipoprotein (a) Level: a 2-Year Follow-Up Study. J Lipid Atheroscler. 2019;8(1):58-66. PubMed
- Kimura H, Umemori Y, Yuki D. Anaphylactic shock-like symptoms due to niacin overdose: A case report. J Dermatol 2022;49(8):e287-e288. PubMed
- Nawaz N, Mistretta T, Karime C, Lewis J, Wolf E. Cholestatic Drug-Induced Liver Injury in a Patient Taking High-Dose Niacin for Hyperlipidemia. J Investig Med High Impact Case Rep 2024;12:23247096231224349. PubMed
Vitamin B12 30 references
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Hartman TJ, Woodson K, Stolzenberg-Solomon R, et al. Association of the B-vitamins pyridoxal 5'-phosphate (B6), B12, and folate with lung cancer risk in older men. Am J Epidemiol 2001;153:688-94.. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Lange H, Suryapranata H, De Luca G, et al. Folate therapy and in-stent restenosis after coronary stenting. N Engl J Med 2004;350:2673-81. PubMed
- Collin, S. M., Metcalfe, C., Refsum, H., Lewis, S. J., Zuccolo, L., Smith, G. D., Chen, L., Harris, R., Davis, M., Marsden, G., Johnston, C., Lane, J. A., Ebbing, M., Bonaa, K. H., Nygard, O., Ueland, P. M., Grau, M. V., Baron, J. A., Donovan, J. L., Nea
- Geissbuhler, P., Mermillod, B., and Rapin, C. H. Elevated serum vitamin B12 levels associated with CRP as a predictive factor of mortality in palliative care cancer patients: a prospective study over five years. J.Pain Symptom.Manage. 2000;20(2):93-103. PubMed
- Salles, N., Herrmann, F., Sakbani, K., Rapin, C. H., and Sieber, C. High vitamin B12 level: a strong predictor of mortality in elderly inpatients. J Am Geriatr.Soc 2005;53(5):917-918.
- Looker, H. C., Fagot-Campagna, A., Gunter, E. W., Pfeiffer, C. M., Sievers, M. L., Bennett, P. H., Nelson, R. G., Hanson, R. L., and Knowler, W. C. Homocysteine and vitamin B(12) concentrations and mortality rates in type 2 diabetes. Diabetes Metab Res R
- Uhl, W., Nolting, A., Golor, G., Rost, K. L., and Kovar, A. Safety of hydroxocobalamin in healthy volunteers in a randomized, placebo-controlled study. Clin Toxicol (Phila) 2006;44 Suppl 1:17-28. PubMed
- Borron, S. W., Baud, F. J., Barriot, P., Imbert, M., and Bismuth, C. Prospective study of hydroxocobalamin for acute cyanide poisoning in smoke inhalation. Ann Emerg.Med 2007;49(6):794-801, 801. PubMed
- Borron, S. W., Baud, F. J., Megarbane, B., and Bismuth, C. Hydroxocobalamin for severe acute cyanide poisoning by ingestion or inhalation. Am J Emerg.Med 2007;25(5):551-558. PubMed
- Lewis, J. G. Gout, Steatorrhoea, and Megaloblastic Anaemia. Ann Rheum.Dis 1962;21(3):284-286. PubMed
- Tal, S., Shavit, Y., Stern, F., and Malnick, S. Association between vitamin B12 levels and mortality in hospitalized older adults. J Am Geriatr.Soc 2010;58(3):523-526. PubMed
- Baztan, J. J., Gavidia, J. J., Gomez-Pavon, J., Esteve, A., and Ruiperez, I. High vitamin B12 levels and in-hospital mortality. J Am Geriatr.Soc 2010;58(11):2237-2238. PubMed
- Omboni, E., Checchini, M., and Longoni, F. [Hypopotassemia and megaloblastic anemia. Presentation of a case]. Minerva Med 8-31-1987;78(16):1255-1257.
- Aalfs As, Scholvinck LH, Horvath B. Acneiform eruption in a 5-year old due to vitamin B12 supplementation. Eur J Dermatol 2013;23(5):726-7. PubMed
- Balta I, Ozuguz P. Vitamin B12-induced acneiform eruption. Cutan Ocul Toxicol 2014;33(2):94-5. PubMed
- Carman KB, Belgemen T, Yis U. Involuntary movements misdiagnosed as seizure during vitamin B12 treatment. Pediatr Emerg Care 2013;29(11):1223-4. PubMed
- Djuric V, Bogic M, Popadic AP, et al. Anaphylactic reaction to hydroxycobalamin with tolerance to cyanocobalamin. Ann Allergy Asthma Immunol 2012;108(3):207-8. PubMed
- Kartel O, Gulec M, Demirel F, et al. Vitamin B12 allergy and successful desensitization with cyanocobalamin: A case report. Allergol Immunopath (Madr) 2012;40(5):324-5.
- Patiroglu T, Unal E, Yildirim S. Infantile tremor syndrome associated with cobalamin therapy: A case report. Clin Neurol Neurosurg 2013;115(9):1903-5. PubMed
- Schulte S, Barkema LW, Kardaun SH. Long-lasting atypical acneiform eruption with prominent comedones induced by hydroxocobalamin (vitamin B12). J Dtsch Dermatol Ges 2014;12(6):502-3.
- Zanus C, Alberini E, Costa P, et al. Involuntary movements after correction of vitamin B12 deficiency: A video-case report. Epileptic Disord 2012;14(2):174-80. PubMed
- Fanidi A, Carreras-Torres R, Larose TL, et al. Is high vitamin B12 status a cause of lung cancer? Int J Cancer. 2019 Sep 15;145(6):1499-1503. PubMed
- Fujita Y, Mizukami T, Maya Y, et al. Vitamin B12 allergy manifesting as lymphomatoid contact dermatitis. Eur J Dermatol. 2020;30(3):304-305. PubMed
- Dépret F, Hoffmann C, Daoud L, et al. Association between hydroxocobalamin administration and acute kidney injury after smoke inhalation: a multicenter retrospective study. Crit Care. 2019;23(1):421. PubMed
- Khairan P, Sobue T, Eshak ES, et al. Association of dietary intakes of vitamin B12, vitamin B6, folate, and methionine with the risk of esophageal cancer: the Japan Public Health Center-based (JPHC) prospective study. BMC Cancer 2021;21(1):982. PubMed
- Evans J, Pandya A, Ding Y, Qunibi WY. Hydroxocobalamin-Induced Oxalate Nephropathy in a Patient With Smoke Inhalation. Kidney Int Rep 2021;6(8):2228-2231. PubMed
- Lacombe V, Chabrun F, Lacout C, et al. Persistent elevation of plasma vitamin B12 is strongly associated with solid cancer. Sci Rep 2021;11(1):13361. PubMed
- Pegalajar-García MD, Cebolla-Verdugo M, Prados-Carmona Á, Llamas-Segura C, Navarro-Triviño FJ. Systemic allergic dermatitis to cobalt present in cyanocobalamin supplementation. Contact Dermatitis 2023;89(3):203-205. PubMed
Black Pepper 29 references
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
- Bano G, Amla V, Raina RK, et al. The effect of piperine on pharmacokinetics of phenytoin in healthy volunteers. Planta Med 1987;53:568-9. PubMed
- Bano G, et al. Effect of piperine on bioavailability and pharmacokinetics of propranolol and theophylline in healthy volunteers. Eur J Clin Pharmacol 1991;41;615-7. PubMed
- Cohle SD, Trestrail JD III, Graham MA, et al. Fatal pepper aspiration. Am J Dis Child 1988;142:633-6. PubMed
- Bhardwaj RK, Glaeser H, Becquemont L, et al. Piperine, a major constituent of black pepper, inhibits human P-glycoprotein and CYP3A4. J Pharmacol Exp Ther 2002;302:645-50. PubMed
- Velpandian T, Jasuja R, Bhardwaj RK, et al. Piperine in food: interference in the pharmacokinetics of phenytoin. Eur J Drug Metab Pharmacokinet 2001;26:241-7. PubMed
- Pattanaik S, Hota D, Prabhakar S, et al. Pharmacokinetic interaction of a single dose of piperine with steady-state carbamazepine in epilepsy patients. Phytother Res 2009;23:1281-6.
- Munakata, M., Kobayashi, K., Niisato-Nezu, J., Tanaka, S., Kakisaka, Y., Ebihara, T., Ebihara, S., Haginoya, K., Tsuchiya, S., and Onuma, A. Olfactory stimulation using black pepper oil facilitates oral feeding in pediatric patients receiving long-term en
- Myers, B. M., Smith, J. L., and Graham, D. Y. Effect of red pepper and black pepper on the stomach. Am J Gastroenterol 1987;82(3):211-214.
- Raghavendra, R. H. and Naidu, K. A. Spice active principles as the inhibitors of human platelet aggregation and thromboxane biosynthesis. Prostaglandins Leukot.Essent.Fatty Acids 2009;81(1):73-78. PubMed
- Subehan, Usia, T., Kadota, S., and Tezuka, Y. Mechanism-based inhibition of human liver microsomal cytochrome P450 2D6 (CYP2D6) by alkamides of Piper nigrum. Planta Med 2006;72(6):527-532.
- Kasibhatta, R. and Naidu, M. U. Influence of piperine on the pharmacokinetics of nevirapine under fasting conditions: a randomised, crossover, placebo-controlled study. Drugs R.D. 2007;8(6):383-391. PubMed
- Usia, T., Iwata, H., Hiratsuka, A., Watabe, T., Kadota, S., and Tezuka, Y. CYP3A4 and CYP2D6 inhibitory activities of Indonesian medicinal plants. Phytomedicine. 2006;13(1-2):67-73. PubMed
- Mujumdar, A. M., Dhuley, J. N., Deshmukh, V. K., Raman, P. H., Thorat, S. L., and Naik, S. R. Effect of piperine on pentobarbitone induced hypnosis in rats. Indian J Exp.Biol. 1990;28(5):486-487.
- Panda, S. and Kar, A. Piperine lowers the serum concentrations of thyroid hormones, glucose and hepatic 5'D activity in adult male mice. Horm.Metab Res. 2003;35(9):523-526. PubMed
- Lawless, H. and Stevens, D. A. Effects of oral chemical irritation on taste. Physiol Behav. 1984;32(6):995-998. PubMed
- Hiwale, A. R., Dhuley, J. N., and Naik, S. R. Effect of co-administration of piperine on pharmacokinetics of beta-lactam antibiotics in rats. Indian J Exp.Biol. 2002;40(3):277-281.
- Han, Y., Chin Tan, T. M., and Lim, L. Y. In vitro and in vivo evaluation of the effects of piperine on P-gp function and expression. Toxicol.Appl.Pharmacol. 8-1-2008;230(3):283-289. PubMed
- Sharma, P., Varma, M. V., Chawla, H. P., and Panchagnula, R. In situ and in vivo efficacy of peroral absorption enhancers in rats and correlation to in vitro mechanistic studies. Farmaco 2005;60(11-12):874-883. PubMed
- Aher, S., Biradar, S., Gopu, C. L., and Paradkar, A. Novel pepper extract for enhanced P-glycoprotein inhibition. J Pharm.Pharmacol. 2009;61(9):1179-1186. PubMed
- Zutshi, R. K., Singh, R., Zutshi, U., Johri, R. K., and Atal, C. K. Influence of piperine on rifampicin blood levels in patients of pulmonary tuberculosis. J Assoc.Physicians India 1985;33(3):223-224.
- Marotta, R. B. and Floch, M. H. Diet and nutrition in ulcer disease. Med Clin North Am 1991;75(4):967-979. PubMed
- Subehan, Usia, T., Iwata, H., Kadota, S., and Tezuka, Y. Mechanism-based inhibition of CYP3A4 and CYP2D6 by Indonesian medicinal plants. J Ethnopharmacol. 5-24-2006;105(3):449-455. PubMed
- Gimenez L, Zacharisen M. Severe pepper allergy in a young child. WMJ. 2011 Jun;110(3):138-9.
- Ren T, Yang M, Xiao M, Zhu J, Xie W, Zuo Z. Time-dependent inhibition of carbamazepine metabolism by piperine in anti-epileptic treatment. Life Sci. 2019;218:314-323. PubMed
- Thomas AB, Choudhary DC, Raje A, Nagrik SS. Pharmacokinetics and pharmacodynamic herb-drug interaction of piperine with atorvastatin in rats. J Chromatogr Sci 2021;59(4):371-80. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Lin F, Hu Y, Zhang Y, Zhao L, Zhong D, Liu J. Predicting Food-Drug Interactions between Piperine and CYP3A4 Substrate Drugs Using PBPK Modeling. Int J Mol Sci 2024;25(20):10955. PubMed
Magnesium 82 references
- Rodin SM, Johnson BF. Pharmacokinetic interactions with digoxin. Clin Pharmacokinet 1988;15:227-44.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Dahle LO, Berg G, Hammar M, et al. The effect of oral magnesium substitution on pregnancy-induced leg cramps. Am J Obstet Gynecol 1995;173:175-80. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Peikert A, Wilimzig C, Kohne-Volland R. Prophylaxis of migraine with oral magnesium: results from a prospective, multi-center, placebo-controlled and double-blind randomized study. Cephalalgia 1996;16:257-63. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Washington, DC: National Academy Press, 1999. Available at: http://books.nap.edu/books/0309063507/html/index.html.
- Birrer RB, Shallash AJ, Totten V. Hypermagnesemia-induced fatality following epsom salt gargles. J Emerg Med 2002;22:185-8. PubMed
- Ryan MP. Diuretics and potassium/magnesium depletion. Directions for treatment. Am J Med 1987;82:38-47.. PubMed
- Hollifield JW. Magnesium depletion, diuretics, and arrhythmias. Am J Med 1987;82:30-7.. PubMed
- Heidenreich O. Mode of action of conventional and potassium-sparing diuretics--aspects with relevance to Mg-sparing effects. Magnesium 1984;3:248-56..
- Pfaffenrath V, Wessely P, Meyer C, et al. Magnesium in the prophylaxis of migraine--a double-blind placebo-controlled study. Cephalalgia 1996;16:436-40.. PubMed
- Wang F, Van Den Eeden SK, Ackerson LM, et al. Oral magnesium oxide prophylaxis of frequent migrainous headache in children: a randomized, double-blind, placebo-controlled trial. Headache 2003;43:601-10.. PubMed
- Sompolinsky D, Samra Z. Influence of magnesium and manganese on some biological and physical properties of tetracycline. J Bacteriol 1972;110:468-76.. PubMed
- Jeyabalan A, Caritis SN. Pharmacologic inhibition of preterm labor. Clin Obstet Gynecol 2002;45:99-113. PubMed
- Mittendorf R, Dambrosia J, Pryde PG, et al. Association between the use of antenatal magnesium sulfate in preterm labor and adverse health outcomes in infants. Am J Obstet Gynecol 2002;186:1111-8.. PubMed
- Witlin AG, Sibai BM. Magnesium sulfate therapy in preeclampsia and eclampsia. Obstet Gynecol 1998;92:883-9.. DOI
- Crowther CA, Hiller JE, Doyle LW. Magnesium sulphate for preventing preterm birth in threatened preterm labour. Cochrane Database Syst Rev 2002;4:CD001060. . PubMed
- Davey MJ, Teubner D. A randomized controlled trial of magnesium sulfate, in addition to usual care, for rate control in atrial fibrillation. Ann Emerg Med 2005;45:347-53.. PubMed
- L'Hommedieu CS, Nicholas D, Armes DA, et al. Potentiation of magnesium sulfate--induced neuromuscular weakness by gentamicin, tobramycin, and amikacin. J Pediatr 1983;102:629-31..
- Dunn CJ, Goa KL. Risedronate: a review of its pharmacological properties and clinical use in resorptive bone disease. Drugs 2001;61:685-712..
- Kass L, Weekes J, Carpenter L. Effect of magnesium supplementation on blood pressure: a meta-analysis. Eur J Clin Nutr 2012;66:411-8. PubMed
- Koontz SL, Friedman SA, Schwartz ML. Symptomatic hypocalcemia after tocolytic therapy with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 2004;190(6):1773-6. PubMed
- Snyder SW, Cardwell MS. Neuromuscular blockade with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 1989;161(1):35-6. PubMed
- Waisman GD, Mayorga LM, Cámera MI, et al. Magnesium plus nifedipine: potentiation of hypotensive effect in preeclampsia? Am J Obstet Gynecol. 1988;159(2):308-9. PubMed
- Brown DD, Juhl RP. Decreased bioavailability of digoxin due to antacids and kaolin-pectin. N Engl J Med. 1976;295(19):1034-7. PubMed
- Allen MD, Greenblatt DJ, Harmatz JS, et al. Effect of magnesium--aluminum hydroxide and kaolin--pectin on absorption of digoxin from tablets and capsules. J Clin Pharmacol. 1981;21(1):26-30. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an in vitro study. Thromb Haemost. 1996;76(1):88-93. DOI
- Ravn HB, Kristensen SD, Vissinger H, et al. Magnesium inhibits human platelets. Blood Coagul Fibrinolysis. 1996;7(2):241-4. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an infusion study in healthy volunteers. Thromb Haemost. 1996;75(6):939-44. DOI
- Neuvonen PJ, Kivistö KT. The effects of magnesium hydroxide on the absorption and efficacy of two glibenclamide preparations. Br J Clin Pharmacol. 1991;32(2):215-20. PubMed
- Kivistö KT, Neuvonen PJ. Enhancement of absorption and effect of glipizide by magnesium hydroxide. Clin Pharmacol Ther. 1991;49(1):39-43. PubMed
- Neuvonen PJ, Kivistö KT. Enhancement of drug absorption by antacids. An unrecognised drug interaction. Clin Pharmacokinet. 1994;27(2):120-8. PubMed
- Shechter, M., Merz, C. N., Paul-Labrador, M., Meisel, S. R., Rude, R. K., Molloy, M. D., Dwyer, J. H., Shah, P. K., and Kaul, S. Beneficial antithrombotic effects of the association of pharmacological oral magnesium therapy with aspirin in coronary heart
- Ganzevoort, J. W., Hoogerwaard, E. M., and van der Post, J. A. [Hypocalcemic delirium due to magnesium sulphate therapy in a pregnant woman with pre-eclampsia]. Ned.Tijdschr.Geneeskd. 8-3-2002;146(31):1453-1456.
- Horner, S. M. Efficacy of intravenous magnesium in acute myocardial infarction in reducing arrhythmias and mortality. Meta-analysis of magnesium in acute myocardial infarction. Circulation 1992;86(3):774-779. PubMed
- Azria, E., Tsatsaris, V., Goffinet, F., Kayem, G., Mignon, A., and Cabrol, D. [Magnesium sulfate in obstetrics: current data]. J Gynecol.Obstet.Biol.Reprod.(Paris) 2004;33(6 Pt 1):510-517.
- Magee, L. A., Miremadi, S., Li, J., Cheng, C., Ensom, M. H., Carleton, B., Cote, A. M., and von Dadelszen, P. Therapy with both magnesium sulfate and nifedipine does not increase the risk of serious magnesium-related maternal side effects in women with p
- Henyan, N. N., Gillespie, E. L., White, C. M., Kluger, J., and Coleman, C. I. Impact of intravenous magnesium on post-cardiothoracic surgery atrial fibrillation and length of hospital stay: a meta-analysis. Ann.Thorac.Surg. 2005;80(6):2402-2406. PubMed
- Li, J., Zhang, Q., Zhang, M., and Egger, M. Intravenous magnesium for acute myocardial infarction. Cochrane.Database.Syst.Rev. 2007;(2):CD002755. PubMed
- Doyle, L. W., Crowther, C. A., Middleton, P., Marret, S., and Rouse, D. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane.Database.Syst.Rev. 2009;(1):CD004661. PubMed
- Han, S., Crowther, C. A., and Moore, V. Magnesium maintenance therapy for preventing preterm birth after threatened preterm labour. Cochrane.Database.Syst.Rev. 2010;(7):CD000940. PubMed
- Duley, L., Gulmezoglu, A. M., Henderson-Smart, D. J., and Chou, D. Magnesium sulphate and other anticonvulsants for women with pre-eclampsia. Cochrane.Database.Syst.Rev. 2010;(11):CD000025. PubMed
- Conde-Agudelo, A., Romero, R., and Kusanovic, J. P. Nifedipine in the management of preterm labor: a systematic review and metaanalysis. Am J Obstet.Gynecol. 2011;204(2):134-20. PubMed
- Wong, G. K., Boet, R., Poon, W. S., Chan, M. T., Gin, T., Ng, S. C., and Zee, B. C. Intravenous magnesium sulphate for aneurysmal subarachnoid hemorrhage: an updated systemic review and meta-analysis. Crit Care 2011;15(1):R52. PubMed
- Magee, L., Sawchuck, D., Synnes, A., and von, Dadelszen P. SOGC Clinical Practice Guideline. Magnesium sulphate for fetal neuroprotection. J Obstet.Gynaecol.Can. 2011;33(5):516-529.
- Doyle, L. W. Antenatal magnesium sulfate and neuroprotection. Curr Opin Pediatr 2012;24(2):154-159. PubMed
- McDonald, S. D., Lutsiv, O., Dzaja, N., and Duley, L. A systematic review of maternal and infant outcomes following magnesium sulfate for pre-eclampsia/eclampsia in real-world use. Int J Gynaecol.Obstet. 2012;118(2):90-96. PubMed
- Gordon, M., Naidoo, K., Akobeng, A. K., and Thomas, A. G. Osmotic and stimulant laxatives for the management of childhood constipation. Cochrane.Database.Syst.Rev. 2012;7:CD009118. PubMed
- Dodd, J. M., Crowther, C. A., and Middleton, P. Oral betamimetics for maintenance therapy after threatened preterm labour. Cochrane.Database.Syst.Rev. 2012;12:CD003927. PubMed
- Wu, X., Wang, C., Zhu, J., Zhang, C., Zhang, Y., and Gao, Y. Meta-analysis of randomized controlled trials on magnesium in addition to beta-blocker for prevention of postoperative atrial arrhythmias after coronary artery bypass grafting. BMC.Cardiovasc.D PubMed
- Thorp, J. M., Jr., Katz, V. L., Campbell, D., and Cefalo, R. C. Hypersensitivity to magnesium sulfate. Am.J.Obstet.Gynecol. 1989;161(4):889-890. PubMed
- Duley L and Gulmezoglu AM. Magnesium sulphate versus lytic cocktail for eclampsia. Cochrane Database of Systematic Reviews 2000;(3) PubMed
- Gibbins KJ, Browning KR, Lopes VV, Anderson BL, Rouse DJ. Evaluation of the clinical use of magnesium sulfate for cerebral palsy prevention. Obstet Gynecol 2013;121(2 Pt 1):235-40. PubMed
- Ji D. Oral magnesium sulfate causes perforation during bowel preparation for fiberoptic colonoscopy in patients with colorectal cancer. J Emerg Med 2012;43(4):716-7. PubMed
- Yagi T, Naito T, Mino Y, Umemura K, Kawakami J. Impact of concomitant antacid administration on gabapentin plasma exposure and oral bioavailability in healthy adult subjects. Drug Metab Pharmacokinet 2012;27(2):248-54. PubMed
- Yamasaki M, Funakoshi S, Matsuda S, Imazu T, Takeda Y, Murakami T, Maeda Y. Interaction of magnesium oxide with gastric acid secretion inhibitors in clinical pharmacotherapy. Eur J Clin Pharmacol 2014;70(8):921-4. PubMed
- Choi ES, Jeong WJ, Ahn SH, Oh AY, Jeon YT, Do SH. Magnesium sulfate accelerates the onset of low-dose rocuronium in patients undergoing laryngeal microsurgery. J Clin Anesth. 2017 Feb;36:102-106. PubMed
- Ikee R, Toyoyama T, Endo T, Tsunoda M, Hashimoto N. Impact of sevelamer hydrochloride on serum magnesium concentrations in hemodialysis patients. Magnes Res. 2016 Apr 1;29(4):184-90. PubMed
- Miller ES, Sakowicz A, Leger E. Lange E, Yee LM. The association between receipt of intrapartum magnesium and postpartum hemorrhage. Am J Obstet Gynecol 2018;218(1 Suppl):S165.
- Rodríguez-Rubio L, Solis Garcia Del Pozo J, Nava E, Jordán J. Interaction between magnesium sulfate and neuromuscular blockers during the perioperative period. A systematic review and meta-analysis. J Clin Anesth. 2016;34:524-34. PubMed
- Brown RS. Magnesium Sulfate: Another Cause of a Solute Diuresis. Am J Kidney Dis. 2017;69(4):550-551. PubMed
- Park H, Qin R, Smith TJ, et al. North Central Cancer Treatment Group N10C2 (Alliance): a double-blind placebo-controlled study of magnesium supplements to reduce menopausal hot flashes. Menopause. 2015;22(6):627-32. PubMed
- Sakanoue M, Sanada J, Kanekura T. Skin eruption elicited by magnesium oxide (Maglax). J Dermatol. 2016;43(2):221-2.
- Iwamuro M, Saito S, Yoshioka M, et al. A Magnesium Oxide Bezoar. Intern Med. 2018;57(21):3087-3091. PubMed
- Vilchez G, Dai J, Kumar K, Mundy D, Kontopoulos E, Sokol RJ. Racial/ethnic disparities in magnesium sulfate neuroprotection: a subgroup analysis of a multicenter randomized controlled trial. J Matern Fetal Neonatal Med. 2018;31(17):2304-2311. PubMed
- Drug Safety Communication: FDA Recommends Against Prolonged Use of Magnesium Sulfate to Stop Pre-term Labor Due to Bone Changes in Exposed Babies. U.S. Food and Drug Administration (FDA), May 30, 2013. https://www.fda.gov/downloads/Drugs/DrugSafety/UCM353
- Committee Opinion: Magnesium Sulfate Use in Obstetrics. The American College of Obstetricians and Gynecologists Committee on Obstetric Practice Society for Maternal-Fetal Medicine, Number 652, January 2016. https://www.acog.org/Clinical-Guidance-and-Publi
- Kashihara Y, Terao Y, Yoda K, et al. Effects of magnesium oxide on pharmacokinetics of L-dopa/carbidopa and assessment of pharmacodynamic changes by a model-based simulation. Eur J Clin Pharmacol. 2019;75(3):351-361. PubMed
- Shepherd E, Salam RA, Manhas D, et al. Antenatal magnesium sulphate and adverse neonatal outcomes: A systematic review and meta-analysis. PLoS Med. 2019;16(12):e1002988. PubMed
- Hong JY, Hong JY, Choi YS, et al. Antenatal magnesium sulfate treatment and risk of necrotizing enterocolitis in preterm infants born at less than 32 weeks of gestation. Sci Rep. 2020;10(1):12826. PubMed
- Schuh S, Sweeney J, Rumantir M, et al. Effect of nebulized magnesium vs placebo added to albuterol on hospitalization among children with refractory acute asthma treated in the emergency department: a randomized clinical trial. JAMA. 2020;324(20):2038-20 PubMed
- Almeida CED, Carvalho LR, Andrade CVC, Nascimento PD Jr, Barros GAM, Modolo NSP. Effects of magnesium sulphate on the onset time of rocuronium at different doses: a randomized clinical trial. Braz J Anesthesiol. 2021;71(5):482-8. PubMed
- Gochi Valdovinos A, Arriaga-Redondo M, Dejuan Bitriá E, Pérez Rodríguez I, Márquez Isidro E, Blanco Bravo D. Prenatal therapy with magnesium sulphate and intestinal obstruction due to meconium in preterm newborns. An Pediatr (Engl Ed). 2022 Feb;96(2):138- PubMed
- Iio K, Kondo E, Shibata E, et al. Long-term tocolysis with magnesium sulfate as a risk factor for low bone mass: a case series. J Med Cases. 2022 Feb;13(2):47-50. PubMed
- Eiraku K, Uozumi Y, Hieda M, Maruyama T, Nomura H. A senile case of heart failure associated with hypermagnesemia induced by magnesium-containing laxative agent. Geriatr Gerontol Int. 2022;22(10):897-899.
- Enayati A, Gin JH, Sajeev JK, et al. Efficacy of intravenous magnesium for the management of non-post operative atrial fibrillation with rapid ventricular response: A systematic review and meta-analysis. J Cardiovasc Electrophysiol 2023;34(5):1286-1295. PubMed
- Su YH, Luo DC, Pang Y. Effects of intraoperative Magnesium sulfate infusion on emergency agitation during general anesthesia in patients undergoing radical mastectomy: a randomized controlled study. BMC Anesthesiol 2023;23(1):326. PubMed
- Han J, Park HY, Shin HJ, Chung SH, Do SH. Effects of magnesium sulphate on neostigmine-induced recovery from moderate neuromuscular blockade with rocuronium: a randomized controlled trial. Magnes Res 2023;36(2):31-39. PubMed
- Lee AT, Cordova JC, Jamplis RP, Pomicter GR. Posterior Reversible Encephalopathy Syndrome and Eclampsia in the Setting of Magnesium Toxicity: A Case Report. A A Pract 2023;17(11):e01726. PubMed
- Darmawan D, Rengganis I, Rumende CM, et al. Effectiveness and Safety of Nebulized Magnesium as Last Line Treatment in Adults with Acute Asthma Attack: A Systematic Review and Meta-Analysis. Acta Med Indones 2024;56(1):3-12.
- Shepherd ES, Goldsmith S, Doyle LW, et al. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane Database Syst Rev 2024;5(5):CD004661. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Fenugreek 30 references
- Madar Z, Thorne R. Dietary fiber. Prog Food Nutr Sci 1987;11:153-74.
- Sharma RD, Raghuram TC, Rao NS. Effect of fenugreek seeds on blood glucose and serum lipids in type I diabetes. Eur J Clin Nutr 1990;44:301-6.
- Patil SP, Niphadkar PV, Bapat MM. Allergy to fenugreek (Trigonella foenum graecum). Ann Allergy Asthma Immunol 1997;78:297-300. PubMed
- Lambert J, Cormier J. Potential interaction between warfarin and boldo-fenugreek. Pharmacotherapy 2001;21:509-12. PubMed
- Bordia A, Verma SK, Srivastava KC. Effect of ginger (Zingiber officinale Rosc.) and fenugreek (Trigonella foenumgraecum L.) on blood lipids, blood sugar and platelet aggregation in patients with coronary artery disease. Prostaglandins Leukot Essent Fatty PubMed
- Yalcin SS, Tekinalp G, Ozalp I. Peculiar odor of traditional food and maple syrup urine disease. Pediatr Int 1999;41:108-9. PubMed
- Sewell AC, Mosandl A, Bohles H. False diagnosis of maple syrup urine disease owing to ingestion of herbal tea. N Engl J Med 1999;341:769.. PubMed
- Abdo MS, al-Kafawi AA. Experimental studies on the effect of Trigonella foenum-graecum (abstract). Planta Med 1969;17:14-8.
- Gupta A, Gupta R, Lal B. Effect of Trigonella foenum-graecum (fenugreek) seeds on glycaemic control and insulin resistance in type 2 diabetes mellitus: a double blind placebo controlled study. J Assoc Physicians India 2001;49:1057-61.
- Gabay MP. Galactogogues: medications that induce lactation. J Hum Lact 2002;18:274-9. PubMed
- Chevassus H, Gaillard JB, Farret A, et al. A fenugreek seed extract selectively reduces spontaneous fat intake in overweight subjects. Eur J Clin Pharmacol 2010;66(5):449-55. PubMed
- Turkyilmaz C, Onal E, Hirfanoglu IM, et al. The effect of galactagogue herbal tea on breast milk production and short-term catch-up of birth weight in the first week of life. J Altern Complement Med 2011;17(2):139-42. PubMed
- Swafford S, Berens P. Effect of fenugreek on breast milk volume. Abstract presented at: 5th International Meeting of the Academy of Breastfeeding Medicine; September 11-13,2000, Tucson, Arizona.
- Abdel-Barry, J. A., Abdel-Hassan, I. A., Jawad, A. M., and al Hakiem, M. H. Hypoglycaemic effect of aqueous extract of the leaves of Trigonella foenum-graecum in healthy volunteers. East Mediterr.Health J 2000;6(1):83-88. DOI
- Parvizpur, A., Ahmadiani, A., and Kamalinejad, M. Probable role of spinal purinoceptors in the analgesic effect of Trigonella foenum (TFG) leaves extract. J Ethnopharmacol 3-8-2006;104(1-2):108-112. PubMed
- Mora, A., Herrrera, A., Lopez, C., Dahbi, G., Mamani, R., Pita, J. M., Alonso, M. P., Llovo, J., Bernardez, M. I., Blanco, J. E., Blanco, M., and Blanco, J. Characteristics of the Shiga-toxin-producing enteroaggregative Escherichia coli O104:H4 German ou
- Blanco, J. [Stx2a-producing enteroaggregative Escherichia coli O104:H4-ST678. Microbiological diagnostic already, for this and other STEC/VTEC serotypes!]. Enferm.Infecc.Microbiol.Clin. 2012;30(2):84-89.
- Beutin, L. and Martin, A. Outbreak of Shiga toxin-producing Escherichia coli (STEC) O104:H4 infection in Germany causes a paradigm shift with regard to human pathogenicity of STEC strains. J Food Prot. 2012;75(2):408-418. PubMed
- King LA, Nogareda F, Weill FX, Mariani-Kurkdjian P, Loukiadis E, Gault G, Jourdan-DaSilva N, Bingen E, Macé M, Thevenot D, Ong N, Castor C, Noël H, Van Cauteren D, Charron M, Vaillant V, Aldabe B, Goulet V, Delmas G, Couturier E, Le Strat Y, Combe C, Delm
- Reeder C, Legrand A, O'Connor-Von SK. The Effect of Fenugreek on Milk Production and Prolactin Levels in Mothers of Preterm Infants. Clinical Lactation 2013;4(4):159-165. DOI
- Al-Jenoobi FI, Ahad A, Mahrous GM, Al-Mohizea AM, AlKharfy KM, Al-Suwayeh SA. Effects of fenugreek, garden cress, and black seed on theophylline pharmacokinetics in beagle dogs. Pharm Biol 2015;53(2):296-300. PubMed
- Rao A, Steels E, Inder WJ, Abraham S, Vitetta L. Testofen, a specialised Trigonella foenum-graecum seed extract reduces age-related symptoms of androgen decrease, increases testosterone levels and improves sexual function in healthy aging males in a doubl
- Steels E, Rao A, Vitetta L. Physiological aspects of male libido enhanced by standardized Trigonella foenum-graecum extract and mineral formulation. Phytother Res. 2011 Sep;25(9):1294-300.
- Gong J, Fang K, Dong H, Wang D, Hu M, Lu F. Effect of fenugreek on hyperglycaemia and hyperlipidemia in diabetes and prediabetes: A meta-analysis. J Ethnopharmacol. 2016 Dec 24;194:260-268. PubMed
- Ouzir M, El Bairi K, Amzazi S. Toxicological properties of fenugreek (Trigonella foenum graecum). Food Chem Toxicol. 2016 Oct;96:145-54. PubMed
- Khodamoradi K, Khosropanah MH, Ayati Z, et al. The Effects of Fenugreek on Cardiometabolic Risk Factors in Adults: A Systematic Review and Meta-analysis. Complement Ther Med. 2020;52:102416. PubMed
- Alkharfy K, Jan B, Alotaibi K, et al. Clopidogrel-herb Interactions: A Pharmacokinetic and Pharmacodynamic Assessment in a Rat Model. Curr Drug Metab 2021;22(12):969-977. PubMed
- Bin Jardan YA, Ahad A, Raish M, Alam MA, Al-Mohizea AM, Al-Jenoobi FI. Effects of garden cress, fenugreek and black seed on the pharmacodynamics of metoprolol: an herb-drug interaction study in rats with hypertension. Pharm Biol 2021;59(1):1088-1097. PubMed
- Al-Mohizea AM, Ahad A, El-Maghraby GM, et al. Effects of Nigella sativa, Lepidium sativum and Trigonella foenum-graecum on sildenafil disposition in beagle dogs. Eur J Drug Metab Pharmacokinet. 2015;40(2):219-24. PubMed
- Alkharfy KM, Al-Jenoobi FI, Al-Mohizea AM, et al. Effects of Lepidium sativum, Nigella sativa and Trigonella foenum-graceum on phenytoin pharmacokinetics in beagle dogs. Phytother Res. 2013;27(12):1800-4.
Horny Goat Weed 11 references
- Cirigliano MD, Szapary PO. Horny goat weed for erectile dysfunction. Alt Med Alert 2001;4:19-22.
- Partin JF, Pushkin YR. Tachyarrhythmia and hypomania with horny goat weed. Psychosomatics 2004;45:536-7. PubMed
- De Naeyer A, Pocock V, Milligan S, De Keukeleire D. Estrogenic activity of a polyphenolic extract of the leaves of Epimedium brevicornum. Fitoterapia 2005;76:35-40. PubMed
- Zhang CZ, Wang SX, Zhang Y, et al. In vitro estrogenic activities of Chinese medicinal plants traditionally used for the management of menopausal symptoms. J Ethnopharmacol 2005;98:295-300. PubMed
- Yap SP, Shen P, Li J, et al. Molecular and pharmacodynamic properties of estrogenic extracts from the traditional Chinese medicinal herb, Epimedium. J Ethnopharmacol 2007;113:218-24. PubMed
- Yan, F. F., Liu, Y., Liu, Y. F., and Zhao, Y. X. Herba Epimedii water extract elevates estrogen level and improves lipid metabolism in postmenopausal women. Phytother.Res. 2008;22(9):1224-1228. PubMed
- Ramanathan VS, Mitropoulos E, Shlopov B, et al. An Enzyte'ing' case of acute hepatitis. J Clin Gastroenterol 2011;45(9):834-5. PubMed
- Zhong Q, Shi Z, Zhang L, et al. The potential of Epimedium koreanum Nakai for herb-drug interaction. J Pharm Pharmacol 2017;69(10):1398-408. doi: 10.1111/jphp.12773.
- Irfan M, Kwon TH, Lee DH, et al. Antiplatelet and Antithrombotic Effects of Epimedium koreanum Nakai. Evid Based Complement Alternat Med. Apr 2021;2021:7071987. PubMed
- Tan K, Yang W, Pang L, Hou F. Differences in clinical characteristics among 726 patients with Chinese herbal medicine- or Western medicine-induced liver injury. Medicine (Baltimore) 2022;101(32):e29909. PubMed
- Li K, Yu XH, Maskey AR, et al. Cytochrome P450 3A4 suppression by epimedium and active compound kaempferol leads to synergistic anti-inflammatory effect with corticosteroid. Front Pharmacol 2023;13:1042756. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC