
MalicMax Ingredients & Drug Interactions
What is this page for?
First and foremost: checking MalicMax against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
MalicMax is a dietary supplement by Wonder Laboratories with 8 active ingredients. Its ingredients are commonly taken for morning sickness in pregnancy, premenstrual syndrome (pms), preventing or treating b6 deficiency.Based on those ingredients, 1,570 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Ashwagandha, Boswellia Extract, Magnesium. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against MalicMax by Wonder Laboratories
Ask about any prescription or over-the-counter medication and we check it for interactions with MalicMax by Wonder Laboratories — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of MalicMax by Wonder Laboratories
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
MalicMax contains eight active ingredients. Vitamin B6, thiamine, and magnesium are essential nutrients that support energy metabolism and nerve function.
Manganese is a trace mineral involved in bone health and metabolism. Ashwagandha is an herbal adaptogen traditionally used to support stress and sleep.
Malic acid is an organic acid that may support saliva production for dry mouth. Apple pectin is a soluble fiber from apples.
Boswellia extract is an herbal ingredient, although we hold no interaction data for it. The product also contains inactive ingredients (k-gelatin, calcium carbonate, and magnesium stearate) as excipients.
Does it work?
Not established
The strongest evidence supports vitamin B6 for treating sideroblastic anemia and vitamin B6 deficiency itself, and thiamine for thiamine deficiency and Wernicke-Korsakoff syndrome (a serious brain condition linked to alcohol use). Magnesium is effective for constipation, indigestion, and preventing pre-eclampsia in pregnancy.
Vitamin B6 is possibly effective for pregnancy-related nausea. Ashwagandha is possibly effective for insomnia, anxiety, stress, and generalized anxiety disorder, though the long-term evidence is limited.
For the other uses listed — manganese for hay fever or osteoarthritis, malic acid for fatigue or fibromyalgia, and apple pectin for blood sugar control — the evidence we hold is insufficient to rate them, meaning you'd be using the product on limited science. Boswellia's effectiveness is not in our data.
How safe is it?
Well-documented data
Vitamin B6 is well tolerated at doses under 100 mg daily, but high doses (especially above 1,000 mg daily or cumulative totals over 1,000 grams) can cause sensory nerve damage (neuropathy) with long-term use. Thiamine is generally very safe by mouth.
Manganese at normal doses is well tolerated, but high-dose supplements pose a risk of nerve damage, including Parkinson-like symptoms, especially with prolonged use. Ashwagandha is generally well tolerated short-term in healthy adults but has rare reports of liver injury; pregnancy safety data advise against use during pregnancy, and breastfeeding safety is not established.
Magnesium is generally well tolerated orally but can cause diarrhea and gastrointestinal upset; it is safe at normal dietary amounts in pregnancy. Malic acid seems well tolerated in food amounts; long-term supplement safety is not well studied.
Apple pectin is generally safe and well tolerated; rare allergic reactions including anaphylaxis have been reported in sensitive individuals.
Meds to double-check
Major interaction found
Before taking MalicMax, double-check your medications with the tool on this page, especially if you take: blood pressure drugs (antihypertensive medications) — magnesium, vitamin B6, malic acid, and ashwagandha may lower blood pressure further; Parkinson's medication (levodopa/carbidopa or Sinemet) — magnesium substantially reduces its absorption; seizure drugs (phenobarbital or phenytoin) — high-dose vitamin B6 may lower their levels; diabetes drugs (especially insulin or sulfonylureas) — ashwagandha and magnesium may affect blood sugar; sedatives or benzodiazepines — ashwagandha may increase drowsiness; antibiotics (quinolones or tetracyclines) — manganese and magnesium may reduce their absorption; or heart or cholesterol medications (digoxin, lovastatin) — apple pectin may interfere with absorption. If you're unsure about any medication, ask your pharmacist.
The bottom line
Scorecard at a glanceFully disclosed formula with no established evidence rating for its marketed use. Major medication interactions have been identified, and safety information is well characterized.
MalicMax is a multi-ingredient supplement with the strongest evidence for vitamin B6 and thiamine in treating specific deficiencies, and some support for ashwagandha in stress and sleep. If you take blood pressure medications, diabetes drugs, seizure medications, antibiotics, or Parkinson's medications, you must check your specific drugs with the interaction tool on this page before starting.
Talk to your pharmacist or doctor — the product's many ingredients and substantial interaction potential mean a personal review is essential.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 8 of 8 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jul 25, 2024.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about MalicMax, straight from the product label.
| Brand | Wonder Laboratories |
|---|---|
| Barcode (UPC) | 099528802104 |
| Net contents | 100 Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Jul 25, 2024 |
| DSLD ID | 315215 |
| Product type | Other Combinations |
| Supplement form | Capsule |
| Dietary claims / uses | Nutrient, All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Kosher, Gluten Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
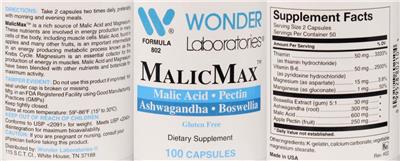
Supplement Facts
The label details for MalicMax by Wonder Laboratories, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Vitamin B6 | 50 mg | 2500% |
| Thiamine | 50 mg | 3333% |
| Manganese | 1 mg | 50% |
| Ashwagandha | 300 mg | -- |
| Magnesium | 15 mg | 3.8% |
| Malic Acid | 600 mg | -- |
| Apple Pectin | 250 mg | -- |
| Boswellia Extract | 30 mg | -- |
Other ingredients: k-Gelatin, Calcium Carbonate, Magnesium Stearate
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Suggested/Recommended/Usage/Directions
Directions: Take 2 capsules two times daily, preferably with morning and evening meals.
Formulation
MalicMax is a rich source of Malic acid and Magnesium. These nutrients are involved in energy production in many cells of the body, including muscle cells. Malic acid, found in apples and many other fruits, is an important intermediate in an energy producing metabolic process known as the Krebs Cycle. Magnesium is an essential cofactor for the production of energy in muscles. Malic acid and Magnesium have been blended with other nutrients and botanicals for maximum activity.
Mfg. in an FDA Registered Facility using Good Manufacturing Practices (GMPs)
Conforms to USP <2091> for weight. Meets USP <2040> disintegration for maximum bioavailability.
Gluten free
Made in USA
Precautions
Tamper evident: Do not use this product if imprinted foil seal under cap is broken or missing.
Keep out of reach of children.
Caution: If you are pregnant or nursing, consult your physician before taking this product.
Storage
Keep tightly closed. Store at room temperature: 59-86 degrees F (15 to 30 degrees C).
Formula
Malic acid Pectin Ashwagandha Boswellia
Ko Kosher Service
FDA Statement of Identity
Dietary Supplement
Seals/Symbols
Ko Kosher Service
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
MalicMax by Wonder Laboratories label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in MalicMax by Wonder Laboratories
These are the 8 active ingredients this product is made of. Select any to open its full monograph.
Serving size2 Capsule(s) Dosage formCapsule Servings per container50 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Vitamin B6
Interacts with210 drugs
Vitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is b...
Vitamin B6 monograph & interactionsThiamine
Interacts with3 drugs
Thiamine (vitamin B1) is an essential nutrient your body needs to turn food into energy and to keep your nerves and heart healthy. Most people get eno...
Thiamine monograph & interactionsManganese
Interacts with83 drugs
Manganese is an essential trace mineral your body needs in small amounts for bone formation, metabolism, and antioxidant defense, and most people get...
Manganese monograph & interactionsAshwagandha
Interacts with1,372 drugs
Ashwagandha is an Ayurvedic herb most often taken to help with stress, anxiety, and sleep, and some small studies suggest it may help, though the evid...
Ashwagandha monograph & interactionsMagnesium
Interacts with295 drugs
Magnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preven...
Magnesium monograph & interactionsMalic Acid
Interacts with172 drugs
Malic acid is a natural acid found in apples and other fruits, often combined with magnesium in supplements marketed for fibromyalgia and muscle pain....
Malic Acid monograph & interactionsApple Pectin
Interacts with23 drugs
Pectin is a natural soluble fiber found in fruits like apples and citrus, and it is widely used in foods and as a fiber supplement. It may modestly he...
Apple Pectin monograph & interactionsBoswellia Extract
Interacts with952 drugs
Boswellia serrata is a tree resin used in traditional medicine, mainly for joint pain and inflammation. Some studies suggest it may help with osteoart...
Boswellia Extract monograph & interactionsOther (inactive) ingredients: K-Gelatin, Calcium Carbonate, Magnesium Stearate. These complete the product’s ingredient list but are not active constituents.
MalicMax by Wonder Laboratories Drug Interactions
HelloPharmacist Interaction Report
MalicMax by Wonder Laboratories contains eight ingredients, seven of which we could check for interactions.
The product does interact with medications — most notably with blood pressure drugs (antihypertensive drugs), which several ingredients may affect. Vitamin B6 and malic acid can theoretically increase the additive blood-pressure-lowering effect, raising the risk of low blood pressure (hypotension).
Ashwagandha carries the same concern. Magnesium is the most serious interaction: it substantially reduces how your body absorbs levodopa/carbidopa (Sinemet), a Parkinson's medication, cutting the drug levels by 35–81%.
Read the full breakdown — every affected drug type, severity by severity
Beyond blood pressure meds, you'll want to check several drug classes. Ashwagandha may amplify sedation from CNS depressants (like benzodiazepines and sleep aids), lower blood sugar too far if you take diabetes drugs, interfere with immune-suppressant medications, and potentially raise thyroid hormone levels if you're on thyroid replacement.
Magnesium can also reduce how well you absorb certain antibiotics (quinolones and tetracyclines), weaken bisphosphonate osteoporosis drugs, and increase the effect of sulfonylurea diabetes medications. Apple pectin may reduce absorption of the cholesterol drug lovastatin, tetracycline antibiotics, and the heart medication digoxin.
Vitamin B6 at high doses can lower levels of the seizure drugs phenobarbital and phenytoin. Manganese may reduce quinolone and tetracycline absorption and theoretically increase risk with antipsychotic medications.
Thiamine and malic acid have limited documented interactions — thiamine with only trimethoprim, and malic acid only with blood pressure medications. We could not check boswellia extract; no interaction data is on file for it.
Altogether, these interactions span 1,515 individual medications. Use the medication checker on this page to verify your exact prescriptions before starting MalicMax.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against MalicMax?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in MalicMax interact with 1,570 drugs. Click any drug to see the details.
8 of the 8 ingredients in MalicMax interact with drugs. Each result below shows which ingredient is responsible. Ashwagandha Boswellia Extract Magnesium Vitamin B6 Malic Acid Manganese Apple Pectin Thiamine
Benserazide, LevodopaMadopar, Prolopa
How Benserazide, Levodopa interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Benserazide, Levodopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Benserazide, Levodopa interactionCarbidopaLodosyn
How Carbidopa interacts with MalicMax — through 1 ingredient. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa interactionCarbidopa, LevodopaDhivy, Rytary, Sinemet, Sinemet CR
How Carbidopa, Levodopa interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa, Levodopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Carbidopa, Levodopa interactionCarbidopa, Levodopa, EntacaponeStalevo
How Carbidopa, Levodopa, Entacapone interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Carbidopa, Levodopa, Entacapone interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Carbidopa, Levodopa, Entacapone interactionLevodopaInbrija, Larodopa
How Levodopa interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Levodopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Levodopa interactionLevodopa, CarbidopaDuodopa
How Levodopa, Carbidopa interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
MagnesiumLevodopa/carbidopa (sinemet) Major
Interaction Summary
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Read the full Magnesium + Levodopa, Carbidopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Levodopa, Carbidopa interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
AshwagandhaHepatotoxic Drugs, Immunosuppressants Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + 6-mercaptopurine interactionBoswellia ExtractImmunosuppressants Moderate
Interaction Summary
Theoretically, Boswellia serrata might alter the effects of immunosuppressive drugs.
Read the full Boswellia Extract + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
Boswellia ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Boswellia Extract + Ado-trastuzumab Emtansine interactionAshwagandhaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with MalicMax — through 1 ingredient. Tap an ingredient for the detail:
AshwagandhaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with MalicMax — through 1 ingredient. Tap an ingredient for the detail:
AshwagandhaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Abacavir, Lamivudine interactionAbemaciclibVerzenio
How Abemaciclib interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
Boswellia ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Boswellia Extract + Abemaciclib interactionAshwagandhaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha + Abemaciclib interactionAbiraterone
How Abiraterone interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
Boswellia ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Boswellia Extract + Abiraterone interactionAshwagandhaHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
AshwagandhaCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha + Abiraterone Acetate interactionBoswellia ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Boswellia Extract + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with MalicMax — through 3 ingredients. Tap an ingredient for the detail:
AshwagandhaImmunosuppressants Moderate
Interaction Summary
Theoretically, taking ashwagandha might decrease the effects of immunosuppressants.
Read the full Ashwagandha + Abrocitinib interactionBoswellia ExtractCytochrome P450 2c9 (cyp2c9) Substrates, Immunosuppressants +1 Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP2C9 substrates.
Read the full Boswellia Extract + Abrocitinib interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
Boswellia ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Boswellia Extract + Acalabrutinib interactionAshwagandhaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with MalicMax — through 1 ingredient. Tap an ingredient for the detail:
AshwagandhaAntidiabetes Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Ashwagandha + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with MalicMax — through 3 ingredients. Tap an ingredient for the detail:
AshwagandhaHepatotoxic Drugs, Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Acebutolol interactionMalic AcidAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, malic acid might increase the risk of hypotension when taken with antihypertensive drugs.
Read the full Malic Acid + Acebutolol interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Acebutolol interactionAcepromazineAtravet
How Acepromazine interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
AshwagandhaCns Depressants Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Ashwagandha + Acepromazine interactionManganeseAntipsychotic Drugs Moderate
Interaction Summary
Theoretically, the risk for manganese toxicity might increase when taken with antipsychotic drugs.
Read the full Manganese + Acepromazine interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
Boswellia ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP1A2 substrates.
Read the full Boswellia Extract + Acetaminophen interactionAshwagandhaCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ashwagandha + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with MalicMax — through 3 ingredients. Tap an ingredient for the detail:
AshwagandhaHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Acetaminophen, Aspirin interactionBoswellia ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP1A2 substrates.
Read the full Boswellia Extract + Acetaminophen, Aspirin interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with MalicMax — through 3 ingredients. Tap an ingredient for the detail:
Boswellia ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP1A2 substrates.
Read the full Boswellia Extract + Acetaminophen, Aspirin, Caffeine interactionAshwagandhaCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ashwagandha + Acetaminophen, Aspirin, Caffeine interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
Boswellia ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP1A2 substrates.
Read the full Boswellia Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAshwagandhaHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, ButalbitalAxocet, Bancap, Bucet, Butex Forte, Esgic CF, Orbivan CF +5 more
How Acetaminophen, Butalbital interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
AshwagandhaCytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ashwagandha + Acetaminophen, Butalbital interactionBoswellia ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP1A2 substrates.
Read the full Boswellia Extract + Acetaminophen, Butalbital interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
Boswellia ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP1A2 substrates.
Read the full Boswellia Extract + Acetaminophen, Butalbital, Caffeine interactionAshwagandhaHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
AshwagandhaCytochrome P450 3a4 (cyp3a4) Substrates, Cns Depressants +2 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ashwagandha + Acetaminophen, Butalbital, Caffeine, Codeine interactionBoswellia ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +1 Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Boswellia Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
Boswellia ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP1A2 substrates.
Read the full Boswellia Extract + Acetaminophen, Butalbital, Codeine interactionAshwagandhaHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
AshwagandhaCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Ashwagandha + Acetaminophen, Butalbital, Codeine Phosphate interactionBoswellia ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP2D6 substrates.
Read the full Boswellia Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
Boswellia ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP1A2 substrates.
Read the full Boswellia Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAshwagandhaHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +2 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ashwagandha + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
AshwagandhaCns Depressants, Cytochrome P450 3a4 (cyp3a4) Substrates +2 Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Ashwagandha + Acetaminophen, Caffeine, Codeine interactionBoswellia ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP2D6 substrates.
Read the full Boswellia Extract + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with MalicMax — through 2 ingredients. Tap an ingredient for the detail:
Boswellia ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, Boswellia serrata might increase the levels of CYP2D6 substrates.
Read the full Boswellia Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAshwagandhaCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +2 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ashwagandha + Acetaminophen, Caffeine, Codeine, Salicylamide interactionEach ingredient & the kinds of drugs it affects
For each ingredient in MalicMax with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Ashwagandha
Antidiabetes Drugs
Theoretically, taking ashwagandha with antidiabetes drugs might increase the risk of hypoglycemia.
There is preliminary clinical evidence suggesting that ashwagandha might lower blood glucose levels. Theoretically, ashwagandha might have additive effects when used with antidiabetes drugs and increase the risk of hypoglycemia.
Antihypertensive Drugs
Theoretically, taking ashwagandha with antihypertensive drugs might increase the risk of hypotension.
Animal research suggests that ashwagandha might lower systolic and diastolic blood pressure. Theoretically, ashwagandha might have additive effects when used with antihypertensive drugs and increase the risk of hypotension.
Benzodiazepines
Theoretically, taking ashwagandha might increase the sedative effects of benzodiazepines.
There is preliminary evidence that ashwagandha might have an additive effect with diazepam (Valium) and clonazepam (Klonopin). This may also occur with other benzodiazepines.
Cns Depressants
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Ashwagandha seems to have sedative effects. Theoretically, this may potentiate the effects of barbiturates, other sedatives, and anxiolytics.
Hepatotoxic Drugs
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Ashwagandha has been linked to cases of acute hepatitis, liver failure, hepatic encephalopathy, autoimmune hepatitis, the need for liver transplantation, and death due to liver failure.
Immunosuppressants
Theoretically, taking ashwagandha might decrease the effects of immunosuppressants.
Ashwagandha has demonstrated immunostimulant effects in humans. Animal research has shown that ashwagandha can attenuate the immunosuppression caused by cyclophosphamide.
Thyroid Hormone
Ashwagandha might increase the effects and adverse effects of thyroid hormone.
Concomitant use of ashwagandha with thyroid hormones may cause additive therapeutic and adverse effects. Preliminary clinical research and animal studies suggest that ashwagandha boosts thyroid hormone synthesis and secretion. In one clinical study, ashwagandha increased triiodothyronine (T3) and thyroxine (T4) levels by 41.5% and 19.6%, respectively, and reduced serum TSH levels by 17.4% from baseline in adults with subclinical hypothyroidism.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
In vitro research shows that ashwagandha extract induces CYP1A2 enzymes.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
In vitro research shows that ashwagandha extract induces CYP3A4 enzymes.
Serotonergic Drugs
Some animal studies have reported that ashwagandha can enhance serotonergic transmission by altering certain serotonin (5-HT) receptors. However, there is no evidence to suggest that ashwagandha increases the risk of serotonin-related effects, and there have been no published case reports of serotonin syndrome when combined with other serotonergic drugs. Nevertheless, due to the lack of extensive studies on the matter and the fact that ashwagandha appears to affect serotonergic pathways, it would be prudent to exercise caution when combining it with drugs that affect serotonin. [References: - Effects of Withania somnifera (Ashwaga ndha) on Stress and the Stress-Related Neuropsychiatric Disorders Anxiety, Depression, and Insomnia. Curr Neuropharmacol. 2021 Sep 14; 19: 1468–1495. - A Prospective, Randomized Double-Blind, Placebo-Controlled Study of Safety and Efficacy of a High-Concentration Full-Spectrum Extract of Ashwagandha Root in Reducing Stress and Anxiety in Adults. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3573577/]
Boswellia Extract
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, Boswellia serrata might increase the levels of CYP1A2 substrates.
In vitro research shows that Boswellia serrata gum resin inhibits CYP1A2 enzymes.
Cytochrome P450 2C19 (Cyp2C19) Substrates
Theoretically, Boswellia serrata might increase the levels of CYP2C19 substrates.
In vitro research shows that Boswellia serrata gum resin inhibits CYP2C19 enzymes.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, Boswellia serrata might increase the levels of CYP2C9 substrates.
In vitro research shows that Boswellia serrata gum resin inhibits CYP2C9 enzymes.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, Boswellia serrata might increase the levels of CYP2D6 substrates.
In vitro research shows that Boswellia serrata gum resin inhibits CYP2D6 enzymes.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, Boswellia serrata might increase or decrease the levels and clinical effects of CYP3A4 substrates.
In vitro research shows that Boswellia serrata gum resin inhibits CYP3A4 enzymes. Other in vitro research shows that Boswellia serrata extract inhibits CYP3A4 enzymes at most concentrations, although it may modestly induce enzyme activity at low concentrations.
Immunosuppressants
Theoretically, Boswellia serrata might alter the effects of immunosuppressive drugs.
Some in vitro research suggests that Boswellia serrata extracts might inhibit mediators of autoimmune disorders such as leukotrienes and reduce production of antibodies and cell-mediated immunity. However, other in vitro research suggests that, when coupled with calcium ions, boswellic acids containing the keto group have immunostimulant properties within specific cell signaling pathways.
Magnesium
Levodopa/Carbidopa (Sinemet)
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Clinical research in healthy volunteers shows that taking magnesium oxide 1000 mg with levodopa 100 mg/carbidopa 10 mg reduces the area under the curve (AUC) of levodopa by 35% and of carbidopa by 81%. In vitro and animal research shows that magnesium produces an alkaline environment in the digestive tract, which might lead to degradation and reduced bioavailability of levodopa/carbidopa.
Aminoglycoside Antibiotics
Concomitant use of aminoglycoside antibiotics and magnesium can increase the risk for neuromuscular weakness.
Both aminoglycosides and magnesium reduce presynaptic acetylcholine release, which can lead to neuromuscular blockade and possible paralysis. This is most likely to occur with high doses of magnesium given intravenously.
Antacids
Use of acid reducers may reduce the laxative effect of magnesium oxide.
A retrospective analysis shows that, in the presence of H2 receptor antagonists (H2RAs) or proton pump inhibitors (PPIs), a higher dose of magnesium oxide is needed for a laxative effect. This may also occur with antacids. Under acidic conditions, magnesium oxide is converted to magnesium chloride and then to magnesium bicarbonate, which has an osmotic laxative effect. By reducing acidity, antacids may reduce the conversion of magnesium oxide to the active bicarbonate salt.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after magnesium containing products.
Bisphosphonates
Magnesium can decrease absorption of bisphosphonates.
Cations, including magnesium, can decrease bisphosphonate absorption. Advise patients to separate doses of magnesium and these drugs by at least 2 hours.
Calcium Channel Blockers
Magnesium can have additive effects with calcium channel blockers, although evidence is conflicting.
Magnesium inhibits calcium entry into smooth muscle cells and may therefore have additive effects with calcium channel blockers. Severe hypotension and neuromuscular blockades may occur when nifedipine is used with intravenous magnesium, although some contradictory evidence suggests that concurrent use of magnesium with nifedipine does not increase the risk of neuromuscular weakness. High doses of magnesium could theoretically have additive effects with other calcium channel blockers.
Digoxin
Magnesium salts may reduce absorption of digoxin.
Clinical evidence suggests that treatment with oral magnesium hydroxide or magnesium trisilicate reduces absorption of digoxin from the intestines. This may reduce the blood levels of digoxin and decrease its therapeutic effects.
Potassium-Sparing Diuretics
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Potassium-sparing diuretics also have magnesium-sparing properties, which can counteract the magnesium losses associated with loop and thiazide diuretics. Theoretically, increased magnesium levels could result from concomitant use of potassium-sparing diuretics and magnesium supplements.
Quinolone Antibiotics
Magnesium decreases absorption of quinolones.
Magnesium can form insoluble complexes with quinolones and decrease their absorption. Advise patients to take these drugs at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Skeletal Muscle Relaxants
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Parenteral magnesium shortens the time to onset of skeletal muscle relaxants by about 1 minute and prolongs the duration of action by about 2 minutes. Magnesium potentiates the effects of skeletal muscle relaxants by decreasing calcium-mediated release of acetylcholine from presynaptic nerve terminals, reducing postsynaptic sensitivity to acetylcholine, and having a direct effect on the membrane potential of myocytes. Magnesium also has vasodilatory actions and increases cardiac output, allowing a greater amount of muscle relaxant to reach the motor end plate. A clinical study found that low-dose rocuronium (0.45 mg/kg), when given after administration of magnesium 30 mg/kg over 10 minutes, has an accelerated onset of effect, which matches the onset of effect seen with a full-dose rocuronium regimen (0.6 mg/kg). In another clinical study, onset times for rocuronium doses of 0.3, 0.6, and 1.2 mg/kg were 86, 76, and 50 seconds, respectively, when given alone, but were reduced to 66, 44, and 38 seconds, respectively, when the doses were given after a 15-minute infusion of magnesium sulfate 60 mg/kg. Giving intraoperative intravenous magnesium sulfate, 50 mg/kg loading dose followed by 15 mg/kg/hour, reduces the onset time of rocuronium, enhances its clinical effects, reduces the dose of intraoperative opiates, and prolongs the spontaneous recovery time. It does not affect the activity of subsequently administered neostigmine.
Sulfonylureas
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Clinical research shows that administration of magnesium hydroxide with glyburide increases glyburide absorption, increases maximal insulin response by 35-fold, and increases the risk of hypoglycemia, when compared with glyburide alone. A similar interaction occurs between magnesium hydroxide and glipizide. The mechanism of this effect appears to be related to the elevation of gastrointestinal pH by magnesium-based antacids, increasing solubility and enhancing absorption of sulfonylureas.
Tetracycline Antibiotics
Magnesium decreases absorption of tetracyclines.
Magnesium can form insoluble complexes with tetracyclines in the gut and decrease their absorption and antibacterial activity. Advise patients to take these drugs 1 hour before or 2 hours after magnesium supplements.
Anticoagulant/Antiplatelet Drugs
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
In vitro evidence shows that magnesium sulfate inhibits platelet aggregation, even at low concentrations. Some preliminary clinical evidence shows that infusion of magnesium sulfate increases bleeding time by 48% and reduces platelet activity. However, other clinical research shows that magnesium does not affect platelet aggregation, although inhibition of platelet-dependent thrombosis can occur.
Gabapentin (Neurontin)
Gabapentin absorption can be decreased by magnesium.
Clinical research shows that giving magnesium oxide orally along with gabapentin decreases the maximum plasma concentration of gabapentin by 33%, time to maximum concentration by 36%, and area under the curve by 43%. Advise patients to take gabapentin at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Sevelamer (Renagel, Renvela)
Sevelamer may increase serum magnesium levels.
In patients on hemodialysis, sevelamer use was associated with a 0.28 mg/dL increase in serum magnesium. The mechanism of this interaction remains unclear.
Vitamin B6
Amiodarone (Cordarone)
Theoretically, vitamin B6 might increase the photosensitivity caused by amiodarone.
Despite initial case reports suggesting that pyridoxine may have a protective effect against amiodarone-induced photosensitivity, preliminary clinical research suggests that pyridoxine may actually exacerbate this adverse effect.
Antihypertensive Drugs
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Research in hypertensive rats shows that vitamin B6 can decrease systolic blood pressure. Similarly, clinical research in patients with hypertension shows that taking high doses of vitamin B6 may reduce systolic and diastolic blood pressure, possibly by reducing plasma levels of epinephrine and norepinephrine.
Phenobarbital (Luminal)
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenobarbital, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenobarbital to avoid high doses of vitamin B6.
Phenytoin (Dilantin)
High doses of vitamin B6 may reduce the levels and clinical effects of phenytoin.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenytoin, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenytoin to avoid high doses of vitamin B6.
Levodopa
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Vitamin B6 (pyridoxine) enhances the metabolism of levodopa, reducing its clinical effects. However, this interaction does not occur when carbidopa is used concurrently with levodopa (Sinemet). Therefore, it is not likely to be a problem in most people.
Malic Acid
Antihypertensive Drugs
Theoretically, malic acid might increase the risk of hypotension when taken with antihypertensive drugs.
Animal research shows that malic acid isolated from tagetes roots can reduce mean arterial blood pressure.
Manganese
Antipsychotic Drugs
Theoretically, the risk for manganese toxicity might increase when taken with antipsychotic drugs.
Hallucinations and behavioral changes have been reported in a patient with liver disease who was taking haloperidol and manganese. Researchers speculate that taking manganese along with haloperidol, phenothiazine-derivatives, or other antipsychotic medications might increase the risk of manganese toxicity in some patients.
Quinolone Antibiotics
Theoretically, manganese might reduce the absorption of quinolone antibiotics.
Manganese is a multivalent cation. Interactions resulting in reduced quinolone absorption have been reported between quinolones and other multivalent cations, such as calcium and iron.
Tetracycline Antibiotics
Theoretically, manganese might reduce the absorption of tetracycline antibiotics.
Manganese is a multivalent cation. Interactions resulting in reduced tetracycline absorption have been reported between tetracyclines and other multivalent cations, such as calcium and iron.
Apple Pectin
Digoxin (Lanoxin)
Theoretically, pectin might reduce the absorption of digoxin, potentially decreasing its effectiveness.
A small clinical study shows that taking digoxin with a kaolin-pectin suspension reduces the absorption of digoxin by about 62%. It is unclear if these effects are due to pectin, kaolin, or the combination.
Lovastatin (Mevacor)
Theoretically, pectin might reduce the absorption of lovastatin, potentially decreasing its effectiveness.
Case reports suggest that concomitant use of pectin and lovastatin might reduce the cholesterol-lowering effect of lovastatin, possibly due to reduced intestinal absorption of lovastatin.
Tetracycline Antibiotics
Theoretically, pectin might reduce the absorption of tetracycline antibiotics, potentially decreasing their effectiveness.
A small clinical study shows that taking tetracycline with bismuth subsalicylate in a kaolin-pectin suspension reduces the absorption of tetracycline by about 34%. It is unclear if these effects are due to pectin, kaolin, bismuth subsalicylate, or the combination.
Thiamine
Trimethoprim (Proloprim)
Trimethoprim might increase blood levels of thiamine.
In vitro, animal, and clinical research suggest that trimethoprim inhibits intestinal thiamine transporter ThTR-2, hepatic transporter OCT1, and renal transporters OCT2, MATE1, and MATE2, resulting in paradoxically increased thiamine plasma concentrations.
Brand information
Manufacturer and brand details for MalicMax, from the product label.
Wonder Laboratories
See all Wonder Laboratories products- Name
- Wonder Laboratories
- Street Address
- 115 S.C.T. Ct.
- City
- White House
- State
- TN
- ZipCode
- 37188
MalicMax by Wonder Laboratories: Common Questions
Does MalicMax by Wonder Laboratories interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take MalicMax if I'm pregnant?
Can I take MalicMax while breastfeeding?
What is ashwagandha in this product for?
Will MalicMax help my dry mouth?
What side effects should I expect?
Is there anything in MalicMax I should know about before I start?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if MalicMax is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind MalicMax’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin B6
Interacts with 210 drugsVitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is best known for helping with pregnancy-rel...
Read the full Vitamin B6 monograph → Herb & supplement monographThiamine
Interacts with 3 drugsThiamine (vitamin B1) is an essential nutrient your body needs to turn food into energy and to keep your nerves and heart healthy. Most people get enough from food, but supplements are clear...
Read the full Thiamine monograph → Herb & supplement monographManganese
Interacts with 83 drugsManganese is an essential trace mineral your body needs in small amounts for bone formation, metabolism, and antioxidant defense, and most people get enough from a normal diet. Supplements m...
Read the full Manganese monograph → Herb & supplement monographAshwagandha
Interacts with 1,372 drugsAshwagandha is an Ayurvedic herb most often taken to help with stress, anxiety, and sleep, and some small studies suggest it may help, though the evidence is still limited. It is generally w...
Read the full Ashwagandha monograph → Herb & supplement monographMagnesium
Interacts with 295 drugsMagnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preventing or correcting deficiency. Some othe...
Read the full Magnesium monograph → Herb & supplement monographMalic Acid
Interacts with 172 drugsMalic acid is a natural acid found in apples and other fruits, often combined with magnesium in supplements marketed for fibromyalgia and muscle pain. The evidence for its health benefits is...
Read the full Malic Acid monograph → Herb & supplement monographPectin
Interacts with 23 drugsPectin is a natural soluble fiber found in fruits like apples and citrus, and it is widely used in foods and as a fiber supplement. It may modestly help with cholesterol, blood sugar, and di...
Read the full Pectin monograph → Herb & supplement monographBoswellia Serrata
Interacts with 952 drugsBoswellia serrata is a tree resin used in traditional medicine, mainly for joint pain and inflammation. Some studies suggest it may help with osteoarthritis symptoms, but the overall evidenc...
Read the full Boswellia Serrata monograph →Sources & How We Checked
MalicMax's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 208 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Vitamin B6 32 references
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Geerling BJ, Dagnelie PC, Badart-Smook A, et al. Diet as a risk factor for the development of ulcerative colitis. Am J Gastroenterol 2000;95:1008-13. PubMed
- South M. Neonatal seizures after pyridoxine use -- reply. Lancet 1999;354:2083. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Baxter P, Aicardi J. Neonatal seizures after pyridoxine use. Lancet 1999;354:2082-3. PubMed
- Bendich A, Cohen M. Vitamin B6 safety issues. Ann N Y Acad Sci 1990;585:321-30.
- Schaumburg H, Kaplan J, Windebank A. Sensory neuropathy from pyridoxine abuse. A new megavitamin syndrome. N Engl J Med 1983;309:445-8. PubMed
- Gordon N. Pyridoxine dependency: an update. Dev Med Child Neurol 1997;39:63-5. PubMed
- Lewis PJ. Pain in the hand and wrist. Pyridoxine supplements may help patients with carpal tunnel syndrome. BMJ 1995;310:1534. PubMed
- Kaufman G. Pyridoxine against amiodarone-induced photosensitivity (letter). Lancet 1984;1:51-2. PubMed
- Mulrow JP, Mulrow CD, McKenna WJ. Pyridoxine and amiodarone-induced photosensitivity. Ann Intern Med 1985;103:68-9. PubMed
- Kawada A, Kashima A, Shiraishi H, et al. Pyridoxine-induced photosensitivity and hypophosphatasia. Dermatology 2000;201:356-60.. PubMed
- Vasile A, Goldberg R, Kornberg B. Pyridoxine toxicity: report of a case. J Am Osteopath Assoc 1984;83:790-1. DOI
- Hansson O, Sillanpaa M. Pyridoxine and serum concentration of phenytoin and phenobarbitone. Lancet 1976;1:256. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Chittumma P, Kaewkiattikun K, Wiriyasiriwach B. Comparison of the effectiveness of ginger and vitamin B6 for treatment of nausea and vomiting in early pregnancy: a randomized double-blind controlled trial. J Med Assoc Thai 2007;90:15-20.
- Hatzitolios, A., Iliadis, F., Katsiki, N., and Baltatzi, M. Is the anti-hypertensive effect of dietary supplements via aldehydes reduction evidence based? A systematic review. Clin Exp.Hypertens. 2008;30(7):628-639. PubMed
- Vasdev, S., Ford, C. A., Parai, S., Longerich, L., and Gadag, V. Dietary vitamin B6 supplementation attenuates hypertension in spontaneously hypertensive rats. Mol.Cell Biochem. 1999;200(1-2):155-162.
- de, Vogel S., Dindore, V., van, Engeland M., Goldbohm, R. A., van den Brandt, P. A., and Weijenberg, M. P. Dietary folate, methionine, riboflavin, and vitamin B-6 and risk of sporadic colorectal cancer. J Nutr 2008;138(12):2372-2378. PubMed
- Hagen, I., Nesheim, B. I., and Tuntland, T. No effect of vitamin B-6 against premenstrual tension. A controlled clinical study. Acta Obstet.Gynecol.Scand. 1985;64(8):667-670. PubMed
- Aybak, M., Sermet, A., Ayyildiz, M. O., and Karakilcik, A. Z. Effect of oral pyridoxine hydrochloride supplementation on arterial blood pressure in patients with essential hypertension. Arzneimittelforschung. 1995;45(12):1271-1273.
- Lal, K. J., Dakshinamurti, K., and Thliveris, J. The effect of vitamin B6 on the systolic blood pressure of rats in various animal models of hypertension. J Hypertens. 1996;14(3):355-363. PubMed
- Lauritzen CH, Reuter HD, Repges R, Bohnert K, and Schmidt U. Treatment of premenstrual tension syndrome with Vitex agnus castus. Controlled, double-blind study versus pyridoxine. Phytomed 1997;4(3):183-189. PubMed
- Fonseca VA, Lavery LA, Thethi TK, et al. Metanx in type 2 diabetes with peripheral neuropathy: A randomized trial. Am J Med 2013;126(2):141-9. PubMed
- Hankey GJ, Eikelboom JW, Yi Q, et al. Treatment with B vitamins and incidence of cancer in patients with previous stroke or transient ischemic attack: Results of a randomized placebo-controlled trial. Stroke 2012;43(6):1572-7. PubMed
- Hoyer-Kuhn H, Kohbrok S, Volland R, Franklin J, Hero B, Beck BB, Hoppe B. Vitamin B6 in primary hyperoxaluria I: first prospective trial after 40 years of practice. Clin J Am Soc Nephrol. 2014 Mar;9(3):468-77. PubMed
- Mahmoud A, Tabassum S, Al Enazi S, et al. Amelioration of levetiracetam-induced behavioral side effects by pyridoxine. A randomized double blind controlled study. Pediatr Neurol 2021;119:15-21. PubMed
- Gupta M, Gallante B, Bamberger JN, et al. Prospective randomized evaluation of idiopathic hyperoxaluria treatments. J Endourol 2021;35(12):1844-1851. PubMed
- Li H, Chen M, Liang S, et al. Excessive vitamin B6 during treatment is related to poor prognosis of patients with nasopharyngeal carcinoma: A U-shaped distribution suggests low dose supplement. Clin Nutr 2021;40(4):2293-2300. PubMed
- Tanigawa J, Nabatame S, Tominaga K, et al. High-dose pyridoxine treatment for inherited glycosylphosphatidylinositol deficiency. Brain Dev 2021;43(6):680-687. PubMed
- Committee on Practice Bulletins-Obstetrics. ACOG Practice Bulletin No. 189: Nausea And Vomiting Of Pregnancy. Obstet Gynecol. 2018;131(1):e15-e30. PubMed
Thiamine 7 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Rogovik, A. L., Vohra, S., and Goldman, R. D. Safety considerations and potential interactions of vitamins: should vitamins be considered drugs? Ann.Pharmacother. 2010;44(2):311-324. PubMed
- Arruti N, Bernedo N, Audicana MT, Villarreal O, Uriel O, Muñoz D. Systemic allergic dermatitis caused by thiamine after iontophoresis. Contact Dermatitis. 2013 Dec;69(6):375-6. PubMed
- Thiamine hydrochloride injection package insert. Lake Zurich, IL: Fresenius Kabi, LLC; September 2019.
- Vora B, Wen A, Yee SW, et al. The Effect of Trimethoprim on Thiamine Absorption: A Transporter-Mediated Drug-Nutrient Interaction. Clin Pharmacol Ther 2023;114(2):381-392.
Manganese 21 references
- Hansten PD, Horn JR. Hansten and Horn's Drug Interactions Analysis and Management. Vancouver, CAN:Appl Therapeut, 1999.
- Barrington WW, Angle CR, Willcockson NK, et al. Autonomic function in manganese alloy workers. Environ Res 1998;78:50-8. PubMed
- Hauser RA, Zesiewicz TA, Martinez C, et al. Blood manganese correlates with brain magnetic resonance imaging changes in patients with liver disease. Can J Neurol Sci 1996;23:95-8. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Lee JW. Manganese intoxication. Arch Neurol 2000;57:597-9.. PubMed
- Powers KM, Smith-Weller T, Franklin GM, et al. Parkinson's disease risks associated with dietary iron, manganese, and other nutrient intakes. Neurology 2003;60:1761-6.. PubMed
- McMillan, D. E. A brief history of the neurobehavioral toxicity of manganese: some unanswered questions. Neurotoxicology 1999;20(2-3):499-507.
- Gerber, G. B., Leonard, A., and Hantson, P. Carcinogenicity, mutagenicity and teratogenicity of manganese compounds. Crit Rev Oncol Hematol. 2002;42(1):25-34. PubMed
- Jiang, Y. and Zheng, W. Cardiovascular toxicities upon manganese exposure. Cardiovasc.Toxicol 2005;5(4):345-354. PubMed
- Mehta, R. and Reilly, J. J. Manganese levels in a jaundiced long-term total parenteral nutrition patient: potentiation of haloperidol toxicity? Case report and literature review. JPEN J Parenter.Enteral Nutr 1990;14(4):428-430. PubMed
- Nemery, B. Metal toxicity and the respiratory tract. Eur Respir.J 1990;3(2):202-219. DOI
- Vanek VW, Borum P, Buchman A, et al. A.S.P.E.N. position paper: recommendations for changes in commercially available parenteral multivitamin and multi-trace element products. Nutr Clin Pract. 2012;27:440-491.doi: 10.1177/0884533612446706 PubMed
- Schuh MJ. Possible Parkinson's disease induced by chronic manganese supplement ingestion. Consult Pharm. 2016;31(12):698-703. doi: 10.4140/TCP.n.2016.698. PubMed
- Baker B, Ali A, Isenring L. Recommendations for manganese supplementation to adult patients receiving long-term home parenteral nutrition: an analysis of the supporting evidence. Nutr Clin Pract 2016;31(2):180-5. doi: 10.1177/0884533615591600. PubMed
- Ho CSH, Ho RCM, Quek AML. Chronic manganese toxicity associated with voltage-gated potassium channel complex antibodies in a relapsing neuropsychiatric disorder. Int J Environ Res Public Health 2018;15(4). pii: E783. doi: 10.3390/ijerph15040783. PubMed
- Yamamoto M, Sakurai K, Eguchi A, et al.; Japan Environment and Children's Study Group: Association between blood manganese level during pregnancy and birth size: the Japan environment and children's study (JECS). Environ Res 2019;172:117-26. PubMed
- Li D, Ge X, Liu Z, et al. Association between long-term occupational manganese exposure and bone quality among retired workers. Environ Sci Pollut Res Int 2020;27(1):482-9. PubMed
- Martin KV, Sucharew H, Dietrich KN, et al. Co-exposure to manganese and lead and pediatric neurocognition in East Liverpool, Ohio. Environ Res 2021;202:111644. PubMed
- Racette BA, Nelson G, Dlamini WW, et al. Depression and anxiety in a manganese-exposed community. Neurotoxicology 2021;85:222-33. PubMed
- Ruiz-Azcona L, Fernández-Olmo I, Expósito A, et al. Impact of environmental airborne manganese exposure on cognitive and motor functions in adults: a systematic review and meta-analysis. Int J Environ Res Public Health 2021;18(8):4075. PubMed
- Uyar E, Gurkas E, Aksu AU, et al. Can therapeutic plasma exchange be life-saving in life-threatening manganese intoxication?. Transfus Apher Sci 2022;61(4):103417. PubMed
Ashwagandha 32 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Upton R, ed. Ashwagandha Root (Withania somnifera): Analytical, quality control, and therapuetic monograph. Santa Cruz, CA: American Herbal Pharmacopoeia 2000:1-25.
- Davis L, Kuttan G. Effect of Withania somnifera on cyclophosphamide-induced urotoxicity. Cancer Lett 2000;148:9-17. PubMed
- Davis L, Kuttan G. Suppressive effect of cyclophosphamide-induced toxicity by Withania somnifera extract in mice. J Ethnopharmacol 1998;62:209-14. PubMed
- Mishra LC, Singh BB, Dagenais S. Scientific basis for the therapeutic use of Withania somnifera (ashwagandha): a review. Altern Med Rev 2000;5:334-46. DOI
- Andallu B, Radhika B. Hypoglycemic, diuretic and hypocholesterolemic effect of winter cherry (Withania somnifera, Dunal) root. Indian J Exp Biol 2000;38:607-9.
- Kulkarni RR, Patki PS, Jog VP, et al. Treatment of osteoarthritis with a herbomineral formulation: a double-blind, placebo-controlled, cross-over study. J Ethnopharmacol 1991;33:91-5. PubMed
- Ahumada F, Aspee F, Wikman G, Hancke J. Withania somnifera exract. Its effects on arterial blood pressure in anaesthetized dogs. Phytother Res 1991;5:111-14.
- Panda S, Kar A. Withania somnifera and Bauhinia purpurea in the regulation of circulating thyroid hormone concentrations in female mice. J Ethnopharmacol 1999;67:233-39. PubMed
- Panda S, Kar A. Changes in thyroid hormone concentrations after administration of ashwagandha root extract to adult male mice. J Pharm Pharmacol 1998;50:1065-68. PubMed
- Sehgal, V. N., Verma, P., and Bhattacharya, S. N. Fixed-drug eruption caused by ashwagandha (Withania somnifera): a widely used Ayurvedic drug. Skinmed. 2012;10(1):48-49.
- Agnihotri AP, Sontakke SD, Thawani VR, Saoji A, Goswami VS. Effects of Withania somnifera in patients of schizophrenia: a randomized, double blind, placebo controlled pilot trial study. Indian J Pharmacol. 2013;45(4):417-8. PubMed
- Biswal BM, Sulaiman SA, Ismail HC, Zakaria H, Musa KI. Effect of Withania somnifera (Ashwagandha) on the development of chemotherapy-induced fatigue and quality of life in breast cancer patients. Integr Cancer Ther. 2013;12(4):312-22.
- Sharma AK, Basu I, Singh S. Efficacy and safety of Ashwagandha root extract in subclinical hypothyroid patients: a double-blind, randomized placebo-controlled trial. J Altern Complement Med. 2018 Mar;24(3):243-248. PubMed
- Durg S, Bavage S, Shivaram SB. Withania somnifera (Indian ginseng) in diabetes mellitus: A systematic review and meta-analysis of scientific evidence from experimental research to clinical application. Phytother Res. 2020;34(5):1041-1059.
- Björnsson HK, Björnsson ES, Avula B, et al. Ashwagandha-induced liver injury: A case series from Iceland and the US Drug-Induced Liver Injury Network. Liver Int. 2020;40(4):825-829. PubMed
- Tharakan A, Shukla H, Benny IR, Tharakan M, George L, Koshy S. Immunomodulatory Effect of Withania somnifera (Ashwagandha) Extract-A Randomized, Double-Blind, Placebo Controlled Trial with an Open Label Extension on Healthy Participants. J Clin Med 2021;1 PubMed
- Ireland PJ, Hardy T, Burt AD, Donnelly MC. Drug-induced hepatocellular injury due to herbal supplement ashwagandha. J R Coll Physicians Edinb. 2021;51(4):363-365. PubMed
- Kamal HI, Patel K, Brdak A, Heffernan J, Ahmad N. Ashwagandha as a unique cause of thyrotoxicosis presenting with supraventricular tachycardia. Cureus. 2022 Mar 25;14(3):e23494. PubMed
- Suryawanshi G, Abdallah M, Thomson M, Desai N, Chauhan A, Lim N. Ashwagandha-Associated Acute Liver Failure Requiring Liver Transplantation. Am J Ther 2023;30(1):e80-e83. PubMed
- Pusec CM, Wolsky R, Llerena C, Sura P. A Case of Supplement-Induced Hepatitis. Cureus 2022;14(10):e30433. PubMed
- Ajgaonkar A, Jain M, Debnath K. Efficacy and Safety of Ashwagandha (Withania somnifera) Root Extract for Improvement of Sexual Health in Healthy Women: A Prospective, Randomized, Placebo-Controlled Study. Cureus 2022;14(10):e30787. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Lubarska M, Halasinski P, Hryhorowicz S, et al. Liver Dangers of Herbal Products: A Case Report of Ashwagandha-Induced Liver Injury. Int J Environ Res Public Health 2023;20(5):3921. PubMed
- Tóth M, Benedek AE, Longerich T, Seitz HK. Ashwagandha-induced acute liver injury: A case report. Clin Case Rep 2023;11(3):e7078.
- Bokan G, Glamocanin T, Mavija Z, et al. Herb-Induced Liver Injury by Ayurvedic Ashwagandha as Assessed for Causality by the Updated RUCAM: An Emerging Cause. Pharmaceuticals (Basel) 2023;16(8):1129. PubMed
- Patel PA, Sanborn E, Then R, Williams DM. Recurrent Reversible Cerebral Vasoconstriction Syndrome: A Report of Two Cases. Cureus 2023;15(8):e42992. PubMed
- Majeed M, Nagabhushanam K, Murali A, Vishwanathan DT, Mamidala RV, Mundkur L. A Standardized Withania somniferra (Linn.) Root Extract with Piperine Alleviates the Symptoms of Anxiety and Depression by Increasing Serotonin Levels: A Double-Blind, Randomize
- Philips CA, Valsan A, Theruvath AH, et al. Ashwagandha-induced liver injury-A case series from India and literature review. Hepatol Commun 2023;7(10):e0270. PubMed
- Hayashi M, Hamada H, Azuma SI, Hayashi K. Painless Thyroiditis by Withania somnifera (Ashwagandha). Cureus 2024;16(3):e55352. PubMed
- Vazirani S, Kothari A, Fujimoto J, Gomez M. Supplements Are Not a Synonym for Safe: Suspected Liver Injury From Ashwagandha. Fed Pract 2023;40(9):315-319. PubMed
- Patel M, Newell R, Hillier M, Ramalingam R. Herbal remedies as a potential cause of hypoadrenalism. Br J Hosp Med (Lond) 2024;85(6):1-4. PubMed
Magnesium 82 references
- Rodin SM, Johnson BF. Pharmacokinetic interactions with digoxin. Clin Pharmacokinet 1988;15:227-44.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Dahle LO, Berg G, Hammar M, et al. The effect of oral magnesium substitution on pregnancy-induced leg cramps. Am J Obstet Gynecol 1995;173:175-80. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Peikert A, Wilimzig C, Kohne-Volland R. Prophylaxis of migraine with oral magnesium: results from a prospective, multi-center, placebo-controlled and double-blind randomized study. Cephalalgia 1996;16:257-63. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Washington, DC: National Academy Press, 1999. Available at: http://books.nap.edu/books/0309063507/html/index.html.
- Birrer RB, Shallash AJ, Totten V. Hypermagnesemia-induced fatality following epsom salt gargles. J Emerg Med 2002;22:185-8. PubMed
- Ryan MP. Diuretics and potassium/magnesium depletion. Directions for treatment. Am J Med 1987;82:38-47.. PubMed
- Hollifield JW. Magnesium depletion, diuretics, and arrhythmias. Am J Med 1987;82:30-7.. PubMed
- Heidenreich O. Mode of action of conventional and potassium-sparing diuretics--aspects with relevance to Mg-sparing effects. Magnesium 1984;3:248-56..
- Pfaffenrath V, Wessely P, Meyer C, et al. Magnesium in the prophylaxis of migraine--a double-blind placebo-controlled study. Cephalalgia 1996;16:436-40.. PubMed
- Wang F, Van Den Eeden SK, Ackerson LM, et al. Oral magnesium oxide prophylaxis of frequent migrainous headache in children: a randomized, double-blind, placebo-controlled trial. Headache 2003;43:601-10.. PubMed
- Sompolinsky D, Samra Z. Influence of magnesium and manganese on some biological and physical properties of tetracycline. J Bacteriol 1972;110:468-76.. PubMed
- Jeyabalan A, Caritis SN. Pharmacologic inhibition of preterm labor. Clin Obstet Gynecol 2002;45:99-113. PubMed
- Mittendorf R, Dambrosia J, Pryde PG, et al. Association between the use of antenatal magnesium sulfate in preterm labor and adverse health outcomes in infants. Am J Obstet Gynecol 2002;186:1111-8.. PubMed
- Witlin AG, Sibai BM. Magnesium sulfate therapy in preeclampsia and eclampsia. Obstet Gynecol 1998;92:883-9.. DOI
- Crowther CA, Hiller JE, Doyle LW. Magnesium sulphate for preventing preterm birth in threatened preterm labour. Cochrane Database Syst Rev 2002;4:CD001060. . PubMed
- Davey MJ, Teubner D. A randomized controlled trial of magnesium sulfate, in addition to usual care, for rate control in atrial fibrillation. Ann Emerg Med 2005;45:347-53.. PubMed
- L'Hommedieu CS, Nicholas D, Armes DA, et al. Potentiation of magnesium sulfate--induced neuromuscular weakness by gentamicin, tobramycin, and amikacin. J Pediatr 1983;102:629-31..
- Dunn CJ, Goa KL. Risedronate: a review of its pharmacological properties and clinical use in resorptive bone disease. Drugs 2001;61:685-712..
- Kass L, Weekes J, Carpenter L. Effect of magnesium supplementation on blood pressure: a meta-analysis. Eur J Clin Nutr 2012;66:411-8. PubMed
- Koontz SL, Friedman SA, Schwartz ML. Symptomatic hypocalcemia after tocolytic therapy with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 2004;190(6):1773-6. PubMed
- Snyder SW, Cardwell MS. Neuromuscular blockade with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 1989;161(1):35-6. PubMed
- Waisman GD, Mayorga LM, Cámera MI, et al. Magnesium plus nifedipine: potentiation of hypotensive effect in preeclampsia? Am J Obstet Gynecol. 1988;159(2):308-9. PubMed
- Brown DD, Juhl RP. Decreased bioavailability of digoxin due to antacids and kaolin-pectin. N Engl J Med. 1976;295(19):1034-7. PubMed
- Allen MD, Greenblatt DJ, Harmatz JS, et al. Effect of magnesium--aluminum hydroxide and kaolin--pectin on absorption of digoxin from tablets and capsules. J Clin Pharmacol. 1981;21(1):26-30. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an in vitro study. Thromb Haemost. 1996;76(1):88-93. DOI
- Ravn HB, Kristensen SD, Vissinger H, et al. Magnesium inhibits human platelets. Blood Coagul Fibrinolysis. 1996;7(2):241-4. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an infusion study in healthy volunteers. Thromb Haemost. 1996;75(6):939-44. DOI
- Neuvonen PJ, Kivistö KT. The effects of magnesium hydroxide on the absorption and efficacy of two glibenclamide preparations. Br J Clin Pharmacol. 1991;32(2):215-20. PubMed
- Kivistö KT, Neuvonen PJ. Enhancement of absorption and effect of glipizide by magnesium hydroxide. Clin Pharmacol Ther. 1991;49(1):39-43. PubMed
- Neuvonen PJ, Kivistö KT. Enhancement of drug absorption by antacids. An unrecognised drug interaction. Clin Pharmacokinet. 1994;27(2):120-8. PubMed
- Shechter, M., Merz, C. N., Paul-Labrador, M., Meisel, S. R., Rude, R. K., Molloy, M. D., Dwyer, J. H., Shah, P. K., and Kaul, S. Beneficial antithrombotic effects of the association of pharmacological oral magnesium therapy with aspirin in coronary heart
- Ganzevoort, J. W., Hoogerwaard, E. M., and van der Post, J. A. [Hypocalcemic delirium due to magnesium sulphate therapy in a pregnant woman with pre-eclampsia]. Ned.Tijdschr.Geneeskd. 8-3-2002;146(31):1453-1456.
- Horner, S. M. Efficacy of intravenous magnesium in acute myocardial infarction in reducing arrhythmias and mortality. Meta-analysis of magnesium in acute myocardial infarction. Circulation 1992;86(3):774-779. PubMed
- Azria, E., Tsatsaris, V., Goffinet, F., Kayem, G., Mignon, A., and Cabrol, D. [Magnesium sulfate in obstetrics: current data]. J Gynecol.Obstet.Biol.Reprod.(Paris) 2004;33(6 Pt 1):510-517.
- Magee, L. A., Miremadi, S., Li, J., Cheng, C., Ensom, M. H., Carleton, B., Cote, A. M., and von Dadelszen, P. Therapy with both magnesium sulfate and nifedipine does not increase the risk of serious magnesium-related maternal side effects in women with p
- Henyan, N. N., Gillespie, E. L., White, C. M., Kluger, J., and Coleman, C. I. Impact of intravenous magnesium on post-cardiothoracic surgery atrial fibrillation and length of hospital stay: a meta-analysis. Ann.Thorac.Surg. 2005;80(6):2402-2406. PubMed
- Li, J., Zhang, Q., Zhang, M., and Egger, M. Intravenous magnesium for acute myocardial infarction. Cochrane.Database.Syst.Rev. 2007;(2):CD002755. PubMed
- Doyle, L. W., Crowther, C. A., Middleton, P., Marret, S., and Rouse, D. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane.Database.Syst.Rev. 2009;(1):CD004661. PubMed
- Han, S., Crowther, C. A., and Moore, V. Magnesium maintenance therapy for preventing preterm birth after threatened preterm labour. Cochrane.Database.Syst.Rev. 2010;(7):CD000940. PubMed
- Duley, L., Gulmezoglu, A. M., Henderson-Smart, D. J., and Chou, D. Magnesium sulphate and other anticonvulsants for women with pre-eclampsia. Cochrane.Database.Syst.Rev. 2010;(11):CD000025. PubMed
- Conde-Agudelo, A., Romero, R., and Kusanovic, J. P. Nifedipine in the management of preterm labor: a systematic review and metaanalysis. Am J Obstet.Gynecol. 2011;204(2):134-20. PubMed
- Wong, G. K., Boet, R., Poon, W. S., Chan, M. T., Gin, T., Ng, S. C., and Zee, B. C. Intravenous magnesium sulphate for aneurysmal subarachnoid hemorrhage: an updated systemic review and meta-analysis. Crit Care 2011;15(1):R52. PubMed
- Magee, L., Sawchuck, D., Synnes, A., and von, Dadelszen P. SOGC Clinical Practice Guideline. Magnesium sulphate for fetal neuroprotection. J Obstet.Gynaecol.Can. 2011;33(5):516-529.
- Doyle, L. W. Antenatal magnesium sulfate and neuroprotection. Curr Opin Pediatr 2012;24(2):154-159. PubMed
- McDonald, S. D., Lutsiv, O., Dzaja, N., and Duley, L. A systematic review of maternal and infant outcomes following magnesium sulfate for pre-eclampsia/eclampsia in real-world use. Int J Gynaecol.Obstet. 2012;118(2):90-96. PubMed
- Gordon, M., Naidoo, K., Akobeng, A. K., and Thomas, A. G. Osmotic and stimulant laxatives for the management of childhood constipation. Cochrane.Database.Syst.Rev. 2012;7:CD009118. PubMed
- Dodd, J. M., Crowther, C. A., and Middleton, P. Oral betamimetics for maintenance therapy after threatened preterm labour. Cochrane.Database.Syst.Rev. 2012;12:CD003927. PubMed
- Wu, X., Wang, C., Zhu, J., Zhang, C., Zhang, Y., and Gao, Y. Meta-analysis of randomized controlled trials on magnesium in addition to beta-blocker for prevention of postoperative atrial arrhythmias after coronary artery bypass grafting. BMC.Cardiovasc.D PubMed
- Thorp, J. M., Jr., Katz, V. L., Campbell, D., and Cefalo, R. C. Hypersensitivity to magnesium sulfate. Am.J.Obstet.Gynecol. 1989;161(4):889-890. PubMed
- Duley L and Gulmezoglu AM. Magnesium sulphate versus lytic cocktail for eclampsia. Cochrane Database of Systematic Reviews 2000;(3) PubMed
- Gibbins KJ, Browning KR, Lopes VV, Anderson BL, Rouse DJ. Evaluation of the clinical use of magnesium sulfate for cerebral palsy prevention. Obstet Gynecol 2013;121(2 Pt 1):235-40. PubMed
- Ji D. Oral magnesium sulfate causes perforation during bowel preparation for fiberoptic colonoscopy in patients with colorectal cancer. J Emerg Med 2012;43(4):716-7. PubMed
- Yagi T, Naito T, Mino Y, Umemura K, Kawakami J. Impact of concomitant antacid administration on gabapentin plasma exposure and oral bioavailability in healthy adult subjects. Drug Metab Pharmacokinet 2012;27(2):248-54. PubMed
- Yamasaki M, Funakoshi S, Matsuda S, Imazu T, Takeda Y, Murakami T, Maeda Y. Interaction of magnesium oxide with gastric acid secretion inhibitors in clinical pharmacotherapy. Eur J Clin Pharmacol 2014;70(8):921-4. PubMed
- Choi ES, Jeong WJ, Ahn SH, Oh AY, Jeon YT, Do SH. Magnesium sulfate accelerates the onset of low-dose rocuronium in patients undergoing laryngeal microsurgery. J Clin Anesth. 2017 Feb;36:102-106. PubMed
- Ikee R, Toyoyama T, Endo T, Tsunoda M, Hashimoto N. Impact of sevelamer hydrochloride on serum magnesium concentrations in hemodialysis patients. Magnes Res. 2016 Apr 1;29(4):184-90. PubMed
- Miller ES, Sakowicz A, Leger E. Lange E, Yee LM. The association between receipt of intrapartum magnesium and postpartum hemorrhage. Am J Obstet Gynecol 2018;218(1 Suppl):S165.
- Rodríguez-Rubio L, Solis Garcia Del Pozo J, Nava E, Jordán J. Interaction between magnesium sulfate and neuromuscular blockers during the perioperative period. A systematic review and meta-analysis. J Clin Anesth. 2016;34:524-34. PubMed
- Brown RS. Magnesium Sulfate: Another Cause of a Solute Diuresis. Am J Kidney Dis. 2017;69(4):550-551. PubMed
- Park H, Qin R, Smith TJ, et al. North Central Cancer Treatment Group N10C2 (Alliance): a double-blind placebo-controlled study of magnesium supplements to reduce menopausal hot flashes. Menopause. 2015;22(6):627-32. PubMed
- Sakanoue M, Sanada J, Kanekura T. Skin eruption elicited by magnesium oxide (Maglax). J Dermatol. 2016;43(2):221-2.
- Iwamuro M, Saito S, Yoshioka M, et al. A Magnesium Oxide Bezoar. Intern Med. 2018;57(21):3087-3091. PubMed
- Vilchez G, Dai J, Kumar K, Mundy D, Kontopoulos E, Sokol RJ. Racial/ethnic disparities in magnesium sulfate neuroprotection: a subgroup analysis of a multicenter randomized controlled trial. J Matern Fetal Neonatal Med. 2018;31(17):2304-2311. PubMed
- Drug Safety Communication: FDA Recommends Against Prolonged Use of Magnesium Sulfate to Stop Pre-term Labor Due to Bone Changes in Exposed Babies. U.S. Food and Drug Administration (FDA), May 30, 2013. https://www.fda.gov/downloads/Drugs/DrugSafety/UCM353
- Committee Opinion: Magnesium Sulfate Use in Obstetrics. The American College of Obstetricians and Gynecologists Committee on Obstetric Practice Society for Maternal-Fetal Medicine, Number 652, January 2016. https://www.acog.org/Clinical-Guidance-and-Publi
- Kashihara Y, Terao Y, Yoda K, et al. Effects of magnesium oxide on pharmacokinetics of L-dopa/carbidopa and assessment of pharmacodynamic changes by a model-based simulation. Eur J Clin Pharmacol. 2019;75(3):351-361. PubMed
- Shepherd E, Salam RA, Manhas D, et al. Antenatal magnesium sulphate and adverse neonatal outcomes: A systematic review and meta-analysis. PLoS Med. 2019;16(12):e1002988. PubMed
- Hong JY, Hong JY, Choi YS, et al. Antenatal magnesium sulfate treatment and risk of necrotizing enterocolitis in preterm infants born at less than 32 weeks of gestation. Sci Rep. 2020;10(1):12826. PubMed
- Schuh S, Sweeney J, Rumantir M, et al. Effect of nebulized magnesium vs placebo added to albuterol on hospitalization among children with refractory acute asthma treated in the emergency department: a randomized clinical trial. JAMA. 2020;324(20):2038-20 PubMed
- Almeida CED, Carvalho LR, Andrade CVC, Nascimento PD Jr, Barros GAM, Modolo NSP. Effects of magnesium sulphate on the onset time of rocuronium at different doses: a randomized clinical trial. Braz J Anesthesiol. 2021;71(5):482-8. PubMed
- Gochi Valdovinos A, Arriaga-Redondo M, Dejuan Bitriá E, Pérez Rodríguez I, Márquez Isidro E, Blanco Bravo D. Prenatal therapy with magnesium sulphate and intestinal obstruction due to meconium in preterm newborns. An Pediatr (Engl Ed). 2022 Feb;96(2):138- PubMed
- Iio K, Kondo E, Shibata E, et al. Long-term tocolysis with magnesium sulfate as a risk factor for low bone mass: a case series. J Med Cases. 2022 Feb;13(2):47-50. PubMed
- Eiraku K, Uozumi Y, Hieda M, Maruyama T, Nomura H. A senile case of heart failure associated with hypermagnesemia induced by magnesium-containing laxative agent. Geriatr Gerontol Int. 2022;22(10):897-899.
- Enayati A, Gin JH, Sajeev JK, et al. Efficacy of intravenous magnesium for the management of non-post operative atrial fibrillation with rapid ventricular response: A systematic review and meta-analysis. J Cardiovasc Electrophysiol 2023;34(5):1286-1295. PubMed
- Su YH, Luo DC, Pang Y. Effects of intraoperative Magnesium sulfate infusion on emergency agitation during general anesthesia in patients undergoing radical mastectomy: a randomized controlled study. BMC Anesthesiol 2023;23(1):326. PubMed
- Han J, Park HY, Shin HJ, Chung SH, Do SH. Effects of magnesium sulphate on neostigmine-induced recovery from moderate neuromuscular blockade with rocuronium: a randomized controlled trial. Magnes Res 2023;36(2):31-39. PubMed
- Lee AT, Cordova JC, Jamplis RP, Pomicter GR. Posterior Reversible Encephalopathy Syndrome and Eclampsia in the Setting of Magnesium Toxicity: A Case Report. A A Pract 2023;17(11):e01726. PubMed
- Darmawan D, Rengganis I, Rumende CM, et al. Effectiveness and Safety of Nebulized Magnesium as Last Line Treatment in Adults with Acute Asthma Attack: A Systematic Review and Meta-Analysis. Acta Med Indones 2024;56(1):3-12.
- Shepherd ES, Goldsmith S, Doyle LW, et al. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane Database Syst Rev 2024;5(5):CD004661. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Malic Acid 7 references
- Russell IJ, Michalek JE, Flechas JD, Abraham GE. Treatment of fibromyalgia syndrome with Super Malic: a randomized, double blind, placebo controlled, crossover pilot study. J Rheumatol 1995;22:953-8.
- Fiume, Z. Final report on the safety assessment of malic acid and sodium malate. Int J Toxicol 2001;20 Suppl 1:47-55. PubMed
- Electronic Code of Federal Regulations. Title 21. Part 184 - Direct Food Substances Affirmed as Generally Recognized as Safe. Available at: http://www.ecfr.gov/cgi-bin/text-idx?c=ecfr&sid=786bafc6f6343634fbf79fcdca7061e1&rgn=div5&view=text&node=21:3.0.1.1
- Saleem R, Ahmad M, Naz A, et al. Hypotensive and toxicological study of citric acid and other constituents from Tagetes patula roots. Arch Pharm Res 2004;27(10):1037-42.
- Chiriac A, Brzezinski P. Topical malic acid in combination with citric acid: an option to treat recalcitrant warts. Dermatol Ther. 2015;28(6):336-8. PubMed
- CFR - Code of Federal Regulations Title 21 SUBCHAPTER B. 184.1069 Malic Acid. Food and Drug Administration Department Of Health And Human Services. Updated April 1, 2017. https://www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfcfr/CFRSearch.cfm?fr=184.1069.
- Amended Safety Assessment of Malic Acid and Sodium Malate as Used in Cosmetics. Cosmetic Ingredient Review Expert Panel. Updated May 19, 2017. http://www.cir-safety.org/sites/default/files/malic%20acid.pdf. Accessed January 24, 2018.
Pectin 11 references
- Jaakkola MS, et al. Asthma caused by occupational exposure to pectin. J Allergy Clin Immunol 1997;100:575-6. PubMed
- Westphal W, et al. [Exogenous allergic asthma following pectin exposure-a new occupational allergen]. Pneumologie 1990;44(Suppl 1):337-8.
- Baldwin JL, et al. Pectin-induced occupational asthma. Chest 1993;104:1936-7. PubMed
- Cohen AJ, Forse MS, Tarlo SM. Occupational asthma caused by pectin inhalation during the manufacture of jam. Chest 1993;103:309-11.
- Kraut A, et al. Christmas candy maker's asthma. IgG4-mediated pectin allergy. Chest 1992;102:1605-7. PubMed
- Richter WO, Jacob BG, Schwandt P. Interaction between fibre and lovastatin. Lancet 1991;338:706.
- Albert KS, Ayres JW, DiSanto AR, et al. Influence of kaolin-pectin suspension on digoxin bioavailability. J Pharm Sci 1978;67:1582-6. PubMed
- Albert KS, Welch RD, DeSante KA, et al. Decreased tetracycline bioavailability caused by a bismuth subsalicylate antidiarrheal mixture. J Pharm Sci 1979;68:586-8. PubMed
- Electronic Code of Federal Regulations. Title 21. Part 182 -- Substances Generally Recognized As Safe. Available at: https://www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfcfr/CFRSearch.cfm?CFRPart=182
- Federal Register April 17,2003. Anti-Diarrheal Products for over-the-counter human use; final monograph. Available at: http://www.fda.gov/OHRMS/DOCKETS/98fr/03-9380.pdf (Accessed 27 December 2004).
- Washio K, Nakamura M, Sato N, et al. Anaphylaxis in a pectin- and cashew nut-allergic child caused by a citrus bath. Allergol Int 2022;71(1):155-157. PubMed
Boswellia Serrata 16 references
- Gupta I, Gupta V, Parihar A, et al. Effects of Boswellia serrata gum resin in patients with bronchial asthma: results of a double-blind, placebo-controlled, 6-week clinical study. Eur J Med Res 1998;3:511-4.
- Electronic Code of Federal Regulations. Title 21. Part 182 -- Substances Generally Recognized As Safe. Available at: https://www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfcfr/CFRSearch.cfm?CFRPart=182
- Kimmatkar N, Thawani V, Hingorani L, et al. Efficacy and tolerability of Boswellia serrata extract in treatment of osteoarthritis of knee--a randomized double blind placebo controlled trial. Phytomedicine 2003;10:3-7. PubMed
- Liu JJ, Nilsson A, Oredsson S, et al. Boswellic acids trigger apoptosis via a pathway dependent on caspase-8 activation but independent on Fas/Fas ligand interaction in colon cancer HT-29 cells. Carcinogenesis 2002;23:2087-93. PubMed
- Wildfeuer A, Neu IS, Safayhi H, et al. Effects of boswellic acids extracted from a herbal medicine on the biosynthesis of leukotrienes and the course of experimental autoimmune encephalomyelitis. Arzneimittelforschung 1998;48:668-74.
- Gupta I, Parihar A, Malhotra P, et al. Effects of gum resin of Boswellia serrata in patients with chronic colitis. Planta Med 2001;67:391-5. PubMed
- Sengupta K, Alluri KV, Satish AR, et al. A double blind, randomized, placebo controlled study of the efficacy and safety of 5-Loxin. Arthritis Res Ther 2008;10:R85.
- Sengupta K, Krishnaraju AV, Vishal AA, et al. Comparative efficacy and tolerability of 5-Loxin and Aflapin against osteoarthritis of the knee: a double blind, randomized, placebo controlled clinical study. Int J Med Sci 2010;7:366-77.
- Ernst E. Frankincense: systematic review. BMJ 2008;337:a2813. PubMed
- Kirste S, Treier M, Wehrle SJ, et al. Boswellia serratea extract acts on cerebral edema in patients irradiated for brain tumors: a prospective, randomized, placebo-controlled, double-blind pilot trial. Cancer 2011;117:3788-95.
- Frank A, Unger M. Analysis of frankincense from various Boswellia species with inhibitory activity on human drug metabolising cytochrome P450 enzymes using liquid chromatography mass spectrometry after automated on-line extraction. J Chromatogr A 2006;111 PubMed
- Altmann A, Poeckel D, Fischer L, et al. Coupling of boswellic acid-incuded Ca2+ mobilisation and MAPK activation to lipid metabolism and peroxide formation in human leucocytes. Br J Pharmacol 2004;141:223-32.
- El Fortia, M., Badi, H., Elalem, Kh, Kadiki, O., and Topov, Y. Olibanum bezoar: complication of a traditional popular medicine. East Mediterr.Health J 2006;12(6):927-929.
- Meshkat S, Mahmoodi Baram S, Rajaei S, et al. Boswellia serrata extract shows cognitive benefits in a double-blind, randomized, placebo-controlled pilot clinical trial in individuals who suffered traumatic brain injury. Brain Inj 2022;36(4):553-559. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Valente IVB, Garcia D, Abbott A, et al. The anti-proliferative effects of a frankincense extract in a window of opportunity phase ia clinical trial for patients with breast cancer. Breast Cancer Res Treat 2024;204(3):521-530. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC