
Jacked & Sexy Ingredients & Drug Interactions
by Core Labs X
What is this page for?
First and foremost: checking Jacked & Sexy against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Jacked & Sexy is a dietary supplement by Core Labs X with 28 active ingredients. Its ingredients are commonly taken for treating or preventing b12 deficiency, pernicious anemia, low energy and fatigue.Based on those ingredients, 1,765 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Green Tea, Yohimbine Hydrochloride, Piperine. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Jacked & Sexy by Core Labs X
Ask about any prescription or over-the-counter medication and we check it for interactions with Jacked & Sexy by Core Labs X — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Jacked & Sexy by Core Labs X
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Low disclosure
Jacked & Sexy contains 34 ingredients, including vitamins (B12, B6, niacin), plant extracts (Mucuna pruriens, yohimbe, rhodiola, grape seed, guarana, capsicum), and several stimulant-like compounds (higenamine, synephrine, methyl-synephrine, phenethylamine, hordenine, and others). The product also includes alpha-GPC (a brain-support compound), deanol, and centrophenoxine.
There are no inactive ingredients listed.
Does it work?
Not established
The evidence for most ingredients in this product is limited or absent. Vitamin B12 is effective for B12 deficiency, likely effective for cyanide poisoning, and possibly effective for canker sores and nerve pain.
Vitamin B6 is effective for certain anemias and B6 deficiency. Capsicum is likely effective for nerve pain (postherpetic neuralgia and diabetic neuropathy) and possibly effective for cluster headache and back pain.
Niacin is likely effective for pellagra and possibly effective for metabolic syndrome and certain dyslipidemia. Grape seed extract is possibly effective for chronic venous insufficiency but possibly ineffective for allergies and obesity.
For the remaining ingredients—sulbutiamine, higenamine, alpha-GPC, yohimbe, Mucuna pruriens, guarana, and rhodiola—the evidence is classified as insufficient to rate their effectiveness for the conditions they are marketed for.
How safe is it?
Well-documented data
Vitamin B12 is generally very safe and is needed during pregnancy and breastfeeding. Vitamin B6 is well tolerated at normal doses but high doses over time can damage nerves; it's often used for morning sickness under a doctor's guidance.
Sulbutiamine is generally well tolerated short-term, but safety data advise against use during pregnancy and breastfeeding. Higenamine has cardiac stimulant effects and carries no pregnancy or breastfeeding safety data.
Yohimbe can cause serious heart and blood pressure effects and should be avoided in pregnancy and while breastfeeding. Mucuna pruriens contains L-dopa (an active drug-like compound) and should be avoided during pregnancy; it can lower prolactin and reduce milk supply, so avoid while breastfeeding.
Alpha-GPC has limited long-term safety data and carries no pregnancy or breastfeeding information on file. Guarana is high in caffeine and should be avoided during pregnancy; caffeine passes into breast milk.
Multiple other ingredients—including synephrine, yohimbine, N-methyltyramine, phenethylamine, methylsynephrine, isopropylnorsynephrine, hordenine, deanol, and centrophenoxine—have no or very limited safety data for pregnancy and breastfeeding. The product contains multiple stimulant-like compounds and cardiovascular-active ingredients that warrant caution.
Meds to double-check
Major interaction found
Before taking this product, check your medications if you take any of the following: monoamine oxidase inhibitors (MAOIs; Major severity), ephedrine (Major), levodopa or carbidopa (Major), antihypertensive drugs (blood pressure medications; Moderate to Minor), blood thinners or antiplatelet drugs (Moderate), tricyclic antidepressants (Moderate), antipsychotics (Moderate), anti-seizure drugs such as phenytoin, phenobarbital, valproate, carbamazepine, or felbamate (Moderate), stimulant drugs (Moderate), diabetes medications (Moderate), and medications metabolized by liver enzymes including CYP2D6, CYP3A4, CYP2E1, CYP1A2, and CYP2C9 (Moderate). No interactions are documented for the ingredients we could not check.
The bottom line
Scorecard at a glanceFormula with limited ingredient disclosure with no established evidence rating for its marketed use. Major medication interactions have been identified, and safety information is well characterized.
This is a multi-ingredient stimulant and workout supplement with serious cardiovascular effects and extensive medication interactions. If you take any prescription medications—especially blood pressure drugs, antidepressants, anti-seizure medications, blood thinners, diabetes medications, or heart drugs—check your exact list with the tool on this page before considering this product.
Anyone with heart problems, high blood pressure, or anxiety should talk to their pharmacist or doctor first. Several ingredients are poorly studied in humans, and the combination of stimulants and cardiac-active compounds carries real risk.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 28 of 34 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jun 25, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Jacked & Sexy, straight from the product label.
| Brand | Core Labs X |
|---|---|
| Net contents | 45 Cap(s) |
| Market status | On market |
| Date entered into DSLD | Jun 25, 2025 |
| DSLD ID | 336370 |
| Product type | Other Combinations |
| Supplement form | Capsule |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
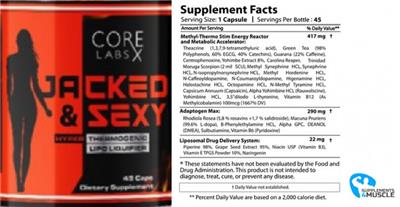
Supplement Facts
The label details for Jacked & Sexy by Core Labs X, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Vitamin B12 | 100 mcg | 1667% |
| Sulbutiamine | 0 NP | -- |
| Vitamin B6 | 0 NP | -- |
| Higenamine Hydrochloride | 0 NP | -- |
| Synephrine Hydrochloride | 0 NP | -- |
| Grape seed extract | 0 NP | -- |
| Alpha Glycerylphosphorylcholine | 0 NP | -- |
| Yohimbine Hydrochloride | 0 NP | -- |
| Naringenin | 0 NP | -- |
| Yohimbe extract | 0 NP | -- |
| Mucuna Pruriens | 0 NP | -- |
| Centrophenoxine | 0 NP | -- |
| N-Caffeoyldopamine | 0 NP | -- |
| N-Coumaroyldopamine | 0 NP | -- |
| Halostachine HCl | 0 NP | -- |
| N Methyl Tyramine HCl | 0 NP | -- |
| B-Phenylethylamine HCl | 0 NP | -- |
| Methyl-Synephrine HCl | 0 NP | -- |
| Deanol | 0 NP | -- |
| N-Isopropylnorsynephrine HCl | 0 NP | -- |
| Methyl Hordenine HCl | 0 NP | -- |
| Capsicum annuum | 0 NP | -- |
| Niacin | 0 NP | -- |
| Guarana | 0 NP | -- |
| Rhodiola rosea | 0 NP | -- |
| Green Tea | 0 NP | -- |
| Methyl-Thermo Stim Energy Reactor and Metabolic Accelerator | 417 mg | -- |
| Theacrine | 0 NP | -- |
| Carolina Reaper | 0 NP | -- |
| Trinidad Moruga Scorpion | 0 NP | -- |
| Octopamine Hydrochloride | 0 NP | -- |
| Alpha-Yohimbine Hydrochloride | 0 NP | -- |
| 3' 5'-Diiodo-L-Thyronine | 0 NP | -- |
| Adaptogen Max | 290 mg | -- |
| Liposomal Drug Delivery System | 22 mg | -- |
| Piperine | 0 NP | -- |
| Vitamin E, Powder | 0 NP | -- |
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formulation
Hyper Thermogenic Lipo Liquifier
Supplements 4 Muscle
FDA Statement of Identity
Dietary Supplement
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure, or prevent any disease.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Jacked & Sexy by Core Labs X label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Jacked & Sexy by Core Labs X
These are the 28 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Capsule(s) Dosage formCapsule Servings per container45 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Methyl-Thermo Stim Energy Reactor and Metabolic Accelerator
- › Vitamin B12
- › Higenamine Hydrochloride
- › Synephrine Hydrochloride
- › Yohimbine Hydrochloride
- › Yohimbe extract
- › Centrophenoxine
- › N-Caffeoyldopamine
- › N-Coumaroyldopamine
- › Halostachine HCl
- › N Methyl Tyramine HCl
- › Methyl-Synephrine HCl
- › N-Isopropylnorsynephrine HCl
- › Methyl Hordenine HCl
- › Capsicum annuum
- › Guarana
- › Green Tea
- › Theacrine
- › Carolina Reaper
- › Trinidad Moruga Scorpion
- › Octopamine Hydrochloride
- › Alpha-Yohimbine Hydrochloride
- › 3' 5'-Diiodo-L-Thyronine
Adaptogen Max
Interacts with327 drugs
Jiaogulan is a climbing vine used in traditional Chinese medicine as an adaptogen and for heart, blood sugar, and cholesterol support. Early human and...
Adaptogen Max monograph & interactionsLiposomal Drug Delivery System
- › Grape seed extract
- › Naringenin
- › Niacin
- › Piperine
- › Vitamin E, Powder
Jacked & Sexy by Core Labs X Drug Interactions
HelloPharmacist Interaction Report
Jacked & Sexy by Core Labs X contains 34 ingredients, many of which interact with medications.
The most serious interaction is with Yohimbe extract and Mucuna Pruriens (cowhage), both of which carry Major-severity interactions: yohimbe with monoamine oxidase inhibitors (MAOIs) can cause a dangerous spike in blood pressure (hypertensive crisis), and cowhage with MAOIs or methyldopa can cause the same. Cowhage also has a Major interaction with levodopa itself, increasing the risk of serious adverse effects.
Read the full breakdown — every affected drug type, severity by severity
Several ingredients affect how your liver processes drugs. Higenamine, grape seed extract, and yohimbe all interact with medications metabolized by cytochrome P450 enzymes (CYP2D6, CYP3A4, and others)—potentially raising drug levels and side effects.
Guarana contains caffeine, which interacts with multiple medications including valproate (epilepsy drug), disulfiram (alcohol-use medication), and clozapine (antipsychotic), and carries a Major interaction with ephedrine.
Additionally, multiple ingredients—yohimbe, higenamine, grape seed extract, rhodiola, capsicum, niacin, and others—may lower blood pressure or interfere with antihypertensive medications. Yohimbe and cowhage also interact with tricyclic antidepressants and stimulant drugs, raising the risk of serious cardiovascular effects.
Grape seed extract, capsicum, niacin, and cowhage interact with blood thinners or antiplatelet drugs, potentially increasing bleeding risk.
Altogether, these interactions span 1,724 individual medications. Several ingredients we could not check—synephrine hydrochloride, yohimbine hydrochloride, naringenin, centrophenoxine, N-caffeoyldopamine, N-coumaroyldopamine, and halostachine HCl—have no interaction data on file.
Use the medication checker on this page to look up your exact prescriptions before taking this product.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Jacked & Sexy?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Jacked & Sexy interact with 1,765 drugs. Click any drug to see the details.
18 of the 28 ingredients in Jacked & Sexy interact with drugs. Each result below shows which ingredient is responsible. Green Tea Yohimbine Hydrochloride Piperine Synephrine Hydrochloride Grape seed extract Higenamine Hydrochloride Vitamin E, Powder Niacin Guarana Octopamine Hydrochloride N Methyl Tyramine HCl N-Isopropylnorsynephrine HCl Methyl Hordenine HCl Adaptogen Max Theacrine Capsicum annuum Methyl-Synephrine HCl Vitamin B12
Aminophylline, Amobarbital, EphedrineAmesec
How Aminophylline, Amobarbital, Ephedrine interacts with Jacked & Sexy — through 12 ingredients. Tap an ingredient for the detail:
GuaranaStimulant Drugs, Ephedrine Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Guarana + Aminophylline, Amobarbital, Ephedrine interactionGreen TeaEphedrine, Stimulant Drugs Major
Interaction Summary
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Read the full Green Tea + Aminophylline, Amobarbital, Ephedrine interactionYohimbe ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, taking yohimbe with stimulant drugs can have additive effects.
Read the full Yohimbe Extract + Aminophylline, Amobarbital, Ephedrine interactionN-isopropylnorsynephrine HclStimulant Drugs Moderate
Interaction Summary
Theoretically, taking isopropylnorsynephrine with stimulant drugs might have additive effects and increase the risk of adverse cardiovascular effects.
Read the full N-isopropylnorsynephrine Hcl + Aminophylline, Amobarbital, Ephedrine interactionTheacrineCns Depressants Moderate
Interaction Summary
Theoretically, theacrine might alter the effects of CNS depressants.
Read the full Theacrine + Aminophylline, Amobarbital, Ephedrine interactionHigenamine HydrochlorideStimulant Drugs Moderate
Interaction Summary
Theoretically, higenamine might increase the risk of cardiovascular toxicity when taken with stimulant drugs.
Read the full Higenamine Hydrochloride + Aminophylline, Amobarbital, Ephedrine interactionMethyl Hordenine HclStimulant Drugs Moderate
Interaction Summary
Hordenine is structurally similar to N-methyltyramine and synephrine, constituents in bitter orange known to have stimulant properties.
Read the full Methyl Hordenine Hcl + Aminophylline, Amobarbital, Ephedrine interactionMethyl-synephrine HclStimulant Drugs Moderate
Interaction Summary
Methylsynephrine has cardiac stimulant effects.
Read the full Methyl-synephrine Hcl + Aminophylline, Amobarbital, Ephedrine interactionSynephrine HydrochlorideStimulant Drugs Moderate
Interaction Summary
Theoretically, bitter orange might increase the risk of hypertension and adverse cardiovascular effects when taken with stimulant drugs.
Read the full Synephrine Hydrochloride + Aminophylline, Amobarbital, Ephedrine interactionRhodiola RoseaCns Depressants Minor
Interaction Summary
Theoretically, rhodiola might increase the risk of adverse effects when taken with CNS depressants.
Read the full Rhodiola Rosea + Aminophylline, Amobarbital, Ephedrine interactionOctopamine HydrochlorideStimulant Drugs Minor
Interaction Summary
Octopamine is thought to have stimulant effects.
Read the full Octopamine Hydrochloride + Aminophylline, Amobarbital, Ephedrine interactionN Methyl Tyramine HclStimulant Drugs Minor
Interaction Summary
N-methyltyramine is thought to have stimulant effects.
Read the full N Methyl Tyramine Hcl + Aminophylline, Amobarbital, Ephedrine interactionAmphetamineAdensys XR-ODT, Adzenys ER, Dyanavel XR, Mydayis
How Amphetamine interacts with Jacked & Sexy — through 14 ingredients. Tap an ingredient for the detail:
Synephrine HydrochlorideStimulant Drugs, Monoamine Oxidase Inhibitors (maois) +1 Major
Interaction Summary
Theoretically, bitter orange might increase the risk of hypertension and adverse cardiovascular effects when taken with stimulant drugs.
Read the full Synephrine Hydrochloride + Amphetamine interactionMucuna PruriensMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens + Amphetamine interactionYohimbe ExtractStimulant Drugs, Monoamine Oxidase Inhibitors (maois) +1 Major
Interaction Summary
Theoretically, taking yohimbe with stimulant drugs can have additive effects.
Read the full Yohimbe Extract + Amphetamine interactionHigenamine HydrochlorideCytochrome P450 2d6 (cyp2d6) Substrates, Stimulant Drugs Moderate
Interaction Summary
Theoretically, higenamine might increase the levels and clinical effects of drugs metabolized by CYP2D6.
Read the full Higenamine Hydrochloride + Amphetamine interactionGrape Seed ExtractCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, grape seed extract may increase the levels of CYP2D6 substrates.
Read the full Grape Seed Extract + Amphetamine interactionGreen TeaStimulant Drugs, Monoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea + Amphetamine interactionPiperineCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Piperine + Amphetamine interactionMethyl Hordenine HclCytochrome P450 2d6 (cyp2d6) Substrates, Stimulant Drugs +1 Moderate
Interaction Summary
Hordenine weakly inhibits cytochrome P450 2D6 (CYP2D6) enzymes in vitro.
Read the full Methyl Hordenine Hcl + Amphetamine interactionMethyl-synephrine HclStimulant Drugs Moderate
Interaction Summary
Methylsynephrine has cardiac stimulant effects.
Read the full Methyl-synephrine Hcl + Amphetamine interactionB-phenylethylamine HclMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, taking phenethylamine concomitantly with MAOIs may increase adverse effects.
Read the full B-phenylethylamine Hcl + Amphetamine interactionGuaranaStimulant Drugs, Monoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Guarana + Amphetamine interactionN-isopropylnorsynephrine HclStimulant Drugs Moderate
Interaction Summary
Theoretically, taking isopropylnorsynephrine with stimulant drugs might have additive effects and increase the risk of adverse cardiovascular effects.
Read the full N-isopropylnorsynephrine Hcl + Amphetamine interactionOctopamine HydrochlorideStimulant Drugs, Monoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Octopamine is thought to have stimulant effects.
Read the full Octopamine Hydrochloride + Amphetamine interactionN Methyl Tyramine HclStimulant Drugs Minor
Interaction Summary
N-methyltyramine is thought to have stimulant effects.
Read the full N Methyl Tyramine Hcl + Amphetamine interactionAtorvastatinAtorvaliq
How Atorvastatin interacts with Jacked & Sexy — through 9 ingredients. Tap an ingredient for the detail:
Green TeaOrganic Anion-transporting Polypeptide Substrates (oatp), Atorvastatin (lipitor) +2 Major
Interaction Summary
Theoretically, green tea might reduce the absorption of organic anion-transporting polypeptide (OATP) substrates.
Read the full Green Tea + Atorvastatin interactionPiperineCytochrome P450 3a4 (cyp3a4) Substrates, Atorvastatin (lipitor) Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Piperine + Atorvastatin interactionGrape Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
Read the full Grape Seed Extract + Atorvastatin interactionSynephrine HydrochlorideCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Bitter orange might increase levels of drugs metabolized by CYP3A4.
Read the full Synephrine Hydrochloride + Atorvastatin interactionHigenamine HydrochlorideCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, higenamine might increase the levels and clinical effects drugs metabolized by CYP3A4.
Read the full Higenamine Hydrochloride + Atorvastatin interactionVitamin E, PowderCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E, Powder + Atorvastatin interactionNiacinHmg-coa Reductase Inhibitors ("statins"), Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and statins might increase the risk of myopathy and rhabdomyolysis in some patients.
Read the full Niacin + Atorvastatin interactionYohimbe ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, yohimbe might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Yohimbe Extract + Atorvastatin interactionRhodiola RoseaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, rhodiola might increase levels of drugs metabolized by CYP3A4.
Read the full Rhodiola Rosea + Atorvastatin interactionAtorvastatin CalciumLipitor
How Atorvastatin Calcium interacts with Jacked & Sexy — through 9 ingredients. Tap an ingredient for the detail:
Green TeaOrganic Anion-transporting Polypeptide Substrates (oatp), Atorvastatin (lipitor) +2 Major
Interaction Summary
Theoretically, green tea might reduce the absorption of organic anion-transporting polypeptide (OATP) substrates.
Read the full Green Tea + Atorvastatin Calcium interactionNiacinHmg-coa Reductase Inhibitors ("statins"), Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and statins might increase the risk of myopathy and rhabdomyolysis in some patients.
Read the full Niacin + Atorvastatin Calcium interactionHigenamine HydrochlorideCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, higenamine might increase the levels and clinical effects drugs metabolized by CYP3A4.
Read the full Higenamine Hydrochloride + Atorvastatin Calcium interactionSynephrine HydrochlorideCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Bitter orange might increase levels of drugs metabolized by CYP3A4.
Read the full Synephrine Hydrochloride + Atorvastatin Calcium interactionPiperineCytochrome P450 3a4 (cyp3a4) Substrates, Atorvastatin (lipitor) Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Piperine + Atorvastatin Calcium interactionGrape Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
Read the full Grape Seed Extract + Atorvastatin Calcium interactionVitamin E, PowderCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E, Powder + Atorvastatin Calcium interactionYohimbe ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, yohimbe might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Yohimbe Extract + Atorvastatin Calcium interactionRhodiola RoseaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, rhodiola might increase levels of drugs metabolized by CYP3A4.
Read the full Rhodiola Rosea + Atorvastatin Calcium interactionBendroflumethiazide, NadololCorzide
How Bendroflumethiazide, Nadolol interacts with Jacked & Sexy — through 9 ingredients. Tap an ingredient for the detail:
Green TeaDiuretic Drugs, Nadolol (corgard) Major
Interaction Summary
Theoretically, using green tea with diuretic drugs might increase the risk of hypokalemia.
Read the full Green Tea + Bendroflumethiazide, Nadolol interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Bendroflumethiazide, Nadolol interactionNiacinAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
Read the full Niacin + Bendroflumethiazide, Nadolol interactionRhodiola RoseaAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking rhodiola with antihypertensive drugs might increase the risk of hypotension.
Read the full Rhodiola Rosea + Bendroflumethiazide, Nadolol interactionGuaranaDiuretic Drugs Moderate
Interaction Summary
Theoretically, using guarana with diuretic drugs might increase the risk of hypokalemia.
Read the full Guarana + Bendroflumethiazide, Nadolol interactionN-isopropylnorsynephrine HclAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, isopropylnorsynephrine might decrease the effects of antihypertensive drugs.
Read the full N-isopropylnorsynephrine Hcl + Bendroflumethiazide, Nadolol interactionOctopamine HydrochlorideAntihypertensive Drugs Moderate
Interaction Summary
In humans, octopamine 450-600 mg daily increases blood pressure in hypotensive patients.
Read the full Octopamine Hydrochloride + Bendroflumethiazide, Nadolol interactionYohimbe ExtractAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, yohimbe might reduce the effects of antihypertensive drugs.
Read the full Yohimbe Extract + Bendroflumethiazide, Nadolol interactionN Methyl Tyramine HclAntihypertensive Drugs Minor
Interaction Summary
In animal research, N-methyltyramine increased blood pressure.
Read the full N Methyl Tyramine Hcl + Bendroflumethiazide, Nadolol interactionBenserazide, LevodopaMadopar, Prolopa
How Benserazide, Levodopa interacts with Jacked & Sexy — through 2 ingredients. Tap an ingredient for the detail:
Mucuna PruriensLevodopa Major
Interaction Summary
Concomitant use can increase the risk of levodopa-related adverse effects.
Read the full Mucuna Pruriens + Benserazide, Levodopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Benserazide, Levodopa interactionCarbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine TannateQuadratuss, Ry Tuss, Rynatuss, Tri Tannate Plus
How Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interacts with Jacked & Sexy — through 16 ingredients. Tap an ingredient for the detail:
Green TeaStimulant Drugs, Ephedrine +1 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionGuaranaEphedrine, Stimulant Drugs Major
Interaction Summary
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Read the full Guarana + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionSynephrine HydrochlorideCytochrome P450 3a4 (cyp3a4) Substrates, Stimulant Drugs Moderate
Interaction Summary
Bitter orange might increase levels of drugs metabolized by CYP3A4.
Read the full Synephrine Hydrochloride + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionHigenamine HydrochlorideCytochrome P450 3a4 (cyp3a4) Substrates, Stimulant Drugs Moderate
Interaction Summary
Theoretically, higenamine might increase the levels and clinical effects drugs metabolized by CYP3A4.
Read the full Higenamine Hydrochloride + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionYohimbe ExtractCytochrome P450 2d6 (cyp2d6) Inhibitors, Stimulant Drugs +1 Moderate
Interaction Summary
CYP2D6 inhibitors may increase the levels and adverse effects of yohimbine, a constituent of yohimbe.
Read the full Yohimbe Extract + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionN-isopropylnorsynephrine HclStimulant Drugs Moderate
Interaction Summary
Theoretically, taking isopropylnorsynephrine with stimulant drugs might have additive effects and increase the risk of adverse cardiovascular effects.
Read the full N-isopropylnorsynephrine Hcl + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionVitamin E, PowderCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E, Powder + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionB-phenylethylamine HclSerotonergic Drugs Moderate
Interaction Summary
Theoretically, combining serotonergic drugs with phenethylamine might increase the risk of serotonergic adverse effects.
Read the full B-phenylethylamine Hcl + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionMethyl-synephrine HclStimulant Drugs Moderate
Interaction Summary
Methylsynephrine has cardiac stimulant effects.
Read the full Methyl-synephrine Hcl + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionMethyl Hordenine HclStimulant Drugs Moderate
Interaction Summary
Hordenine is structurally similar to N-methyltyramine and synephrine, constituents in bitter orange known to have stimulant properties.
Read the full Methyl Hordenine Hcl + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionGrape Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
Read the full Grape Seed Extract + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionPiperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Piperine + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionRhodiola RoseaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, rhodiola might increase levels of drugs metabolized by CYP3A4.
Read the full Rhodiola Rosea + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionDeanolAnticholinergic Drugs Minor
Interaction Summary
Theoretically, deanol might decrease the effectiveness of anticholinergic drugs.
Read the full Deanol + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionN Methyl Tyramine HclStimulant Drugs Minor
Interaction Summary
N-methyltyramine is thought to have stimulant effects.
Read the full N Methyl Tyramine Hcl + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionOctopamine HydrochlorideStimulant Drugs Minor
Interaction Summary
Octopamine is thought to have stimulant effects.
Read the full Octopamine Hydrochloride + Carbetapentane Tannate, Chlorpheniramine Tannate, Ephedrine Tannate, Phenylephrine Tannate interactionCarbidopa, LevodopaDhivy, Rytary, Sinemet, Sinemet CR
How Carbidopa, Levodopa interacts with Jacked & Sexy — through 2 ingredients. Tap an ingredient for the detail:
Mucuna PruriensLevodopa Major
Interaction Summary
Concomitant use can increase the risk of levodopa-related adverse effects.
Read the full Mucuna Pruriens + Carbidopa, Levodopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Carbidopa, Levodopa interactionCarbidopa, Levodopa, EntacaponeStalevo
How Carbidopa, Levodopa, Entacapone interacts with Jacked & Sexy — through 2 ingredients. Tap an ingredient for the detail:
Mucuna PruriensLevodopa Major
Interaction Summary
Concomitant use can increase the risk of levodopa-related adverse effects.
Read the full Mucuna Pruriens + Carbidopa, Levodopa, Entacapone interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Carbidopa, Levodopa, Entacapone interactionChlorothiazide, MethyldopaAldochlor, Aldoclor 150, Aldoclor 250
How Chlorothiazide, Methyldopa interacts with Jacked & Sexy — through 10 ingredients. Tap an ingredient for the detail:
Mucuna PruriensMethyldopa (aldomet) Major
Interaction Summary
Theoretically, concomitant use of cowhage and methyldopa might increase the risk of hypotension.
Read the full Mucuna Pruriens + Chlorothiazide, Methyldopa interactionGreen TeaDiuretic Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, using green tea with diuretic drugs might increase the risk of hypokalemia.
Read the full Green Tea + Chlorothiazide, Methyldopa interactionNiacinAntihypertensive Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
Read the full Niacin + Chlorothiazide, Methyldopa interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Chlorothiazide, Methyldopa interactionYohimbe ExtractAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, yohimbe might reduce the effects of antihypertensive drugs.
Read the full Yohimbe Extract + Chlorothiazide, Methyldopa interactionGuaranaDiuretic Drugs Moderate
Interaction Summary
Theoretically, using guarana with diuretic drugs might increase the risk of hypokalemia.
Read the full Guarana + Chlorothiazide, Methyldopa interactionRhodiola RoseaAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking rhodiola with antihypertensive drugs might increase the risk of hypotension.
Read the full Rhodiola Rosea + Chlorothiazide, Methyldopa interactionN-isopropylnorsynephrine HclAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, isopropylnorsynephrine might decrease the effects of antihypertensive drugs.
Read the full N-isopropylnorsynephrine Hcl + Chlorothiazide, Methyldopa interactionOctopamine HydrochlorideAntihypertensive Drugs Moderate
Interaction Summary
In humans, octopamine 450-600 mg daily increases blood pressure in hypotensive patients.
Read the full Octopamine Hydrochloride + Chlorothiazide, Methyldopa interactionN Methyl Tyramine HclAntihypertensive Drugs Minor
Interaction Summary
In animal research, N-methyltyramine increased blood pressure.
Read the full N Methyl Tyramine Hcl + Chlorothiazide, Methyldopa interactionDyphylline, Ephedrine, Guaifenesin, PhenobarbitalLufyllin-EPG
How Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interacts with Jacked & Sexy — through 13 ingredients. Tap an ingredient for the detail:
GuaranaStimulant Drugs, Phenobarbital (luminal) +1 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Guarana + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionGreen TeaStimulant Drugs, Phenobarbital (luminal) +1 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionTheacrineCns Depressants Moderate
Interaction Summary
Theoretically, theacrine might alter the effects of CNS depressants.
Read the full Theacrine + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionHigenamine HydrochlorideStimulant Drugs Moderate
Interaction Summary
Theoretically, higenamine might increase the risk of cardiovascular toxicity when taken with stimulant drugs.
Read the full Higenamine Hydrochloride + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionMethyl Hordenine HclStimulant Drugs Moderate
Interaction Summary
Hordenine is structurally similar to N-methyltyramine and synephrine, constituents in bitter orange known to have stimulant properties.
Read the full Methyl Hordenine Hcl + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionMethyl-synephrine HclStimulant Drugs Moderate
Interaction Summary
Methylsynephrine has cardiac stimulant effects.
Read the full Methyl-synephrine Hcl + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionSynephrine HydrochlorideStimulant Drugs Moderate
Interaction Summary
Theoretically, bitter orange might increase the risk of hypertension and adverse cardiovascular effects when taken with stimulant drugs.
Read the full Synephrine Hydrochloride + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionN-isopropylnorsynephrine HclStimulant Drugs Moderate
Interaction Summary
Theoretically, taking isopropylnorsynephrine with stimulant drugs might have additive effects and increase the risk of adverse cardiovascular effects.
Read the full N-isopropylnorsynephrine Hcl + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionYohimbe ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, taking yohimbe with stimulant drugs can have additive effects.
Read the full Yohimbe Extract + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionVitamin B6Phenobarbital (luminal) Moderate
Interaction Summary
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Read the full Vitamin B6 + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionRhodiola RoseaCns Depressants Minor
Interaction Summary
Theoretically, rhodiola might increase the risk of adverse effects when taken with CNS depressants.
Read the full Rhodiola Rosea + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionN Methyl Tyramine HclStimulant Drugs Minor
Interaction Summary
N-methyltyramine is thought to have stimulant effects.
Read the full N Methyl Tyramine Hcl + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionOctopamine HydrochlorideStimulant Drugs Minor
Interaction Summary
Octopamine is thought to have stimulant effects.
Read the full Octopamine Hydrochloride + Dyphylline, Ephedrine, Guaifenesin, Phenobarbital interactionEphedrine, Guaifenesin (otc Drug)Ephedrine Formula 400, Ephedrine Plus Tabs
How Ephedrine, Guaifenesin (otc Drug) interacts with Jacked & Sexy — through 10 ingredients. Tap an ingredient for the detail:
Green TeaStimulant Drugs, Ephedrine Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea + Ephedrine, Guaifenesin (otc Drug) interactionGuaranaEphedrine, Stimulant Drugs Major
Interaction Summary
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Read the full Guarana + Ephedrine, Guaifenesin (otc Drug) interactionN-isopropylnorsynephrine HclStimulant Drugs Moderate
Interaction Summary
Theoretically, taking isopropylnorsynephrine with stimulant drugs might have additive effects and increase the risk of adverse cardiovascular effects.
Read the full N-isopropylnorsynephrine Hcl + Ephedrine, Guaifenesin (otc Drug) interactionYohimbe ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, taking yohimbe with stimulant drugs can have additive effects.
Read the full Yohimbe Extract + Ephedrine, Guaifenesin (otc Drug) interactionSynephrine HydrochlorideStimulant Drugs Moderate
Interaction Summary
Theoretically, bitter orange might increase the risk of hypertension and adverse cardiovascular effects when taken with stimulant drugs.
Read the full Synephrine Hydrochloride + Ephedrine, Guaifenesin (otc Drug) interactionMethyl Hordenine HclStimulant Drugs Moderate
Interaction Summary
Hordenine is structurally similar to N-methyltyramine and synephrine, constituents in bitter orange known to have stimulant properties.
Read the full Methyl Hordenine Hcl + Ephedrine, Guaifenesin (otc Drug) interactionMethyl-synephrine HclStimulant Drugs Moderate
Interaction Summary
Methylsynephrine has cardiac stimulant effects.
Read the full Methyl-synephrine Hcl + Ephedrine, Guaifenesin (otc Drug) interactionHigenamine HydrochlorideStimulant Drugs Moderate
Interaction Summary
Theoretically, higenamine might increase the risk of cardiovascular toxicity when taken with stimulant drugs.
Read the full Higenamine Hydrochloride + Ephedrine, Guaifenesin (otc Drug) interactionN Methyl Tyramine HclStimulant Drugs Minor
Interaction Summary
N-methyltyramine is thought to have stimulant effects.
Read the full N Methyl Tyramine Hcl + Ephedrine, Guaifenesin (otc Drug) interactionOctopamine HydrochlorideStimulant Drugs Minor
Interaction Summary
Octopamine is thought to have stimulant effects.
Read the full Octopamine Hydrochloride + Ephedrine, Guaifenesin (otc Drug) interactionEphedrine, Guaifenesin, Phenobarbital, TheophyllineMudrane GG
How Ephedrine, Guaifenesin, Phenobarbital, Theophylline interacts with Jacked & Sexy — through 16 ingredients. Tap an ingredient for the detail:
GuaranaTheophylline, Phenobarbital (luminal) +2 Major
Interaction Summary
Theoretically, guarana might increase the levels and adverse effects of theophylline.
Read the full Guarana + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionGreen TeaPhenobarbital (luminal), Ephedrine +2 Major
Interaction Summary
Theoretically, green tea might reduce the effects of phenobarbital and increase the risk for convulsions.
Read the full Green Tea + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionTrinidad Moruga ScorpionTheophylline Moderate
Interaction Summary
Theoretically, taking capsicum with theophylline might increase the levels and adverse effects of theophylline.
Read the full Trinidad Moruga Scorpion + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionVitamin B6Phenobarbital (luminal) Moderate
Interaction Summary
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Read the full Vitamin B6 + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionSynephrine HydrochlorideStimulant Drugs Moderate
Interaction Summary
Theoretically, bitter orange might increase the risk of hypertension and adverse cardiovascular effects when taken with stimulant drugs.
Read the full Synephrine Hydrochloride + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionYohimbe ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Stimulant Drugs Moderate
Interaction Summary
Theoretically, yohimbe might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Yohimbe Extract + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionPiperineTheophylline, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Black pepper might increase blood levels of theophylline.
Read the full Piperine + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionN-isopropylnorsynephrine HclStimulant Drugs Moderate
Interaction Summary
Theoretically, taking isopropylnorsynephrine with stimulant drugs might have additive effects and increase the risk of adverse cardiovascular effects.
Read the full N-isopropylnorsynephrine Hcl + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionGrape Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, grape juice might reduce the levels of CYP1A2 substrates.
Read the full Grape Seed Extract + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionHigenamine HydrochlorideStimulant Drugs Moderate
Interaction Summary
Theoretically, higenamine might increase the risk of cardiovascular toxicity when taken with stimulant drugs.
Read the full Higenamine Hydrochloride + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionTheacrineCns Depressants Moderate
Interaction Summary
Theoretically, theacrine might alter the effects of CNS depressants.
Read the full Theacrine + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionMethyl-synephrine HclStimulant Drugs Moderate
Interaction Summary
Methylsynephrine has cardiac stimulant effects.
Read the full Methyl-synephrine Hcl + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionMethyl Hordenine HclStimulant Drugs Moderate
Interaction Summary
Hordenine is structurally similar to N-methyltyramine and synephrine, constituents in bitter orange known to have stimulant properties.
Read the full Methyl Hordenine Hcl + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionRhodiola RoseaCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Minor
Interaction Summary
Theoretically, rhodiola might increase levels of drugs metabolized by CYP1A2.
Read the full Rhodiola Rosea + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionOctopamine HydrochlorideStimulant Drugs Minor
Interaction Summary
Octopamine is thought to have stimulant effects.
Read the full Octopamine Hydrochloride + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionN Methyl Tyramine HclStimulant Drugs Minor
Interaction Summary
N-methyltyramine is thought to have stimulant effects.
Read the full N Methyl Tyramine Hcl + Ephedrine, Guaifenesin, Phenobarbital, Theophylline interactionEphedrine, Hydroxyzine, TheophyllineAmi Rax, Marax
How Ephedrine, Hydroxyzine, Theophylline interacts with Jacked & Sexy — through 15 ingredients. Tap an ingredient for the detail:
GuaranaStimulant Drugs, Theophylline +1 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Guarana + Ephedrine, Hydroxyzine, Theophylline interactionGreen TeaStimulant Drugs, Theophylline +1 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea + Ephedrine, Hydroxyzine, Theophylline interactionMethyl Hordenine HclStimulant Drugs Moderate
Interaction Summary
Hordenine is structurally similar to N-methyltyramine and synephrine, constituents in bitter orange known to have stimulant properties.
Read the full Methyl Hordenine Hcl + Ephedrine, Hydroxyzine, Theophylline interactionHigenamine HydrochlorideStimulant Drugs Moderate
Interaction Summary
Theoretically, higenamine might increase the risk of cardiovascular toxicity when taken with stimulant drugs.
Read the full Higenamine Hydrochloride + Ephedrine, Hydroxyzine, Theophylline interactionMethyl-synephrine HclStimulant Drugs Moderate
Interaction Summary
Methylsynephrine has cardiac stimulant effects.
Read the full Methyl-synephrine Hcl + Ephedrine, Hydroxyzine, Theophylline interactionN-isopropylnorsynephrine HclStimulant Drugs Moderate
Interaction Summary
Theoretically, taking isopropylnorsynephrine with stimulant drugs might have additive effects and increase the risk of adverse cardiovascular effects.
Read the full N-isopropylnorsynephrine Hcl + Ephedrine, Hydroxyzine, Theophylline interactionYohimbe ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Stimulant Drugs Moderate
Interaction Summary
Theoretically, yohimbe might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Yohimbe Extract + Ephedrine, Hydroxyzine, Theophylline interactionTrinidad Moruga ScorpionTheophylline Moderate
Interaction Summary
Theoretically, taking capsicum with theophylline might increase the levels and adverse effects of theophylline.
Read the full Trinidad Moruga Scorpion + Ephedrine, Hydroxyzine, Theophylline interactionSynephrine HydrochlorideStimulant Drugs Moderate
Interaction Summary
Theoretically, bitter orange might increase the risk of hypertension and adverse cardiovascular effects when taken with stimulant drugs.
Read the full Synephrine Hydrochloride + Ephedrine, Hydroxyzine, Theophylline interactionPiperineTheophylline, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Black pepper might increase blood levels of theophylline.
Read the full Piperine + Ephedrine, Hydroxyzine, Theophylline interactionGrape Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, grape juice might reduce the levels of CYP1A2 substrates.
Read the full Grape Seed Extract + Ephedrine, Hydroxyzine, Theophylline interactionOctopamine HydrochlorideStimulant Drugs Minor
Interaction Summary
Octopamine is thought to have stimulant effects.
Read the full Octopamine Hydrochloride + Ephedrine, Hydroxyzine, Theophylline interactionN Methyl Tyramine HclStimulant Drugs Minor
Interaction Summary
N-methyltyramine is thought to have stimulant effects.
Read the full N Methyl Tyramine Hcl + Ephedrine, Hydroxyzine, Theophylline interactionDeanolAnticholinergic Drugs Minor
Interaction Summary
Theoretically, deanol might decrease the effectiveness of anticholinergic drugs.
Read the full Deanol + Ephedrine, Hydroxyzine, Theophylline interactionRhodiola RoseaCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rhodiola might increase levels of drugs metabolized by CYP1A2.
Read the full Rhodiola Rosea + Ephedrine, Hydroxyzine, Theophylline interactionEphedrine, Phenobarbital, Potassium Iodide, TheophyllineMudrane, Quadrinal
How Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interacts with Jacked & Sexy — through 15 ingredients. Tap an ingredient for the detail:
Green TeaPhenobarbital (luminal), Ephedrine +2 Major
Interaction Summary
Theoretically, green tea might reduce the effects of phenobarbital and increase the risk for convulsions.
Read the full Green Tea + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionGuaranaEphedrine, Stimulant Drugs +2 Major
Interaction Summary
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Read the full Guarana + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionSynephrine HydrochlorideStimulant Drugs Moderate
Interaction Summary
Theoretically, bitter orange might increase the risk of hypertension and adverse cardiovascular effects when taken with stimulant drugs.
Read the full Synephrine Hydrochloride + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionYohimbe ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, taking yohimbe with stimulant drugs can have additive effects.
Read the full Yohimbe Extract + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionMethyl-synephrine HclStimulant Drugs Moderate
Interaction Summary
Methylsynephrine has cardiac stimulant effects.
Read the full Methyl-synephrine Hcl + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionMethyl Hordenine HclStimulant Drugs Moderate
Interaction Summary
Hordenine is structurally similar to N-methyltyramine and synephrine, constituents in bitter orange known to have stimulant properties.
Read the full Methyl Hordenine Hcl + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionHigenamine HydrochlorideStimulant Drugs Moderate
Interaction Summary
Theoretically, higenamine might increase the risk of cardiovascular toxicity when taken with stimulant drugs.
Read the full Higenamine Hydrochloride + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionTheacrineCns Depressants Moderate
Interaction Summary
Theoretically, theacrine might alter the effects of CNS depressants.
Read the full Theacrine + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionN-isopropylnorsynephrine HclStimulant Drugs Moderate
Interaction Summary
Theoretically, taking isopropylnorsynephrine with stimulant drugs might have additive effects and increase the risk of adverse cardiovascular effects.
Read the full N-isopropylnorsynephrine Hcl + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionTrinidad Moruga ScorpionTheophylline Moderate
Interaction Summary
Theoretically, taking capsicum with theophylline might increase the levels and adverse effects of theophylline.
Read the full Trinidad Moruga Scorpion + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionVitamin B6Phenobarbital (luminal) Moderate
Interaction Summary
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Read the full Vitamin B6 + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionPiperineTheophylline Moderate
Interaction Summary
Black pepper might increase blood levels of theophylline.
Read the full Piperine + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionN Methyl Tyramine HclStimulant Drugs Minor
Interaction Summary
N-methyltyramine is thought to have stimulant effects.
Read the full N Methyl Tyramine Hcl + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionOctopamine HydrochlorideStimulant Drugs Minor
Interaction Summary
Octopamine is thought to have stimulant effects.
Read the full Octopamine Hydrochloride + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionRhodiola RoseaCns Depressants Minor
Interaction Summary
Theoretically, rhodiola might increase the risk of adverse effects when taken with CNS depressants.
Read the full Rhodiola Rosea + Ephedrine, Phenobarbital, Potassium Iodide, Theophylline interactionEphedrine, Phenobarbital, TheophyllineTedral
How Ephedrine, Phenobarbital, Theophylline interacts with Jacked & Sexy — through 15 ingredients. Tap an ingredient for the detail:
Green TeaStimulant Drugs, Theophylline +2 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea + Ephedrine, Phenobarbital, Theophylline interactionGuaranaStimulant Drugs, Theophylline +2 Major
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Guarana + Ephedrine, Phenobarbital, Theophylline interactionPiperineTheophylline Moderate
Interaction Summary
Black pepper might increase blood levels of theophylline.
Read the full Piperine + Ephedrine, Phenobarbital, Theophylline interactionN-isopropylnorsynephrine HclStimulant Drugs Moderate
Interaction Summary
Theoretically, taking isopropylnorsynephrine with stimulant drugs might have additive effects and increase the risk of adverse cardiovascular effects.
Read the full N-isopropylnorsynephrine Hcl + Ephedrine, Phenobarbital, Theophylline interactionYohimbe ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, taking yohimbe with stimulant drugs can have additive effects.
Read the full Yohimbe Extract + Ephedrine, Phenobarbital, Theophylline interactionSynephrine HydrochlorideStimulant Drugs Moderate
Interaction Summary
Theoretically, bitter orange might increase the risk of hypertension and adverse cardiovascular effects when taken with stimulant drugs.
Read the full Synephrine Hydrochloride + Ephedrine, Phenobarbital, Theophylline interactionTheacrineCns Depressants Moderate
Interaction Summary
Theoretically, theacrine might alter the effects of CNS depressants.
Read the full Theacrine + Ephedrine, Phenobarbital, Theophylline interactionMethyl-synephrine HclStimulant Drugs Moderate
Interaction Summary
Methylsynephrine has cardiac stimulant effects.
Read the full Methyl-synephrine Hcl + Ephedrine, Phenobarbital, Theophylline interactionHigenamine HydrochlorideStimulant Drugs Moderate
Interaction Summary
Theoretically, higenamine might increase the risk of cardiovascular toxicity when taken with stimulant drugs.
Read the full Higenamine Hydrochloride + Ephedrine, Phenobarbital, Theophylline interactionMethyl Hordenine HclStimulant Drugs Moderate
Interaction Summary
Hordenine is structurally similar to N-methyltyramine and synephrine, constituents in bitter orange known to have stimulant properties.
Read the full Methyl Hordenine Hcl + Ephedrine, Phenobarbital, Theophylline interactionTrinidad Moruga ScorpionTheophylline Moderate
Interaction Summary
Theoretically, taking capsicum with theophylline might increase the levels and adverse effects of theophylline.
Read the full Trinidad Moruga Scorpion + Ephedrine, Phenobarbital, Theophylline interactionVitamin B6Phenobarbital (luminal) Moderate
Interaction Summary
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Read the full Vitamin B6 + Ephedrine, Phenobarbital, Theophylline interactionOctopamine HydrochlorideStimulant Drugs Minor
Interaction Summary
Octopamine is thought to have stimulant effects.
Read the full Octopamine Hydrochloride + Ephedrine, Phenobarbital, Theophylline interactionN Methyl Tyramine HclStimulant Drugs Minor
Interaction Summary
N-methyltyramine is thought to have stimulant effects.
Read the full N Methyl Tyramine Hcl + Ephedrine, Phenobarbital, Theophylline interactionRhodiola RoseaCns Depressants Minor
Interaction Summary
Theoretically, rhodiola might increase the risk of adverse effects when taken with CNS depressants.
Read the full Rhodiola Rosea + Ephedrine, Phenobarbital, Theophylline interactionEzetimibe, AtorvastatinLiptruzet
How Ezetimibe, Atorvastatin interacts with Jacked & Sexy — through 9 ingredients. Tap an ingredient for the detail:
Green TeaOrganic Anion-transporting Polypeptide Substrates (oatp), Atorvastatin (lipitor) +2 Major
Interaction Summary
Theoretically, green tea might reduce the absorption of organic anion-transporting polypeptide (OATP) substrates.
Read the full Green Tea + Ezetimibe, Atorvastatin interactionPiperineAtorvastatin (lipitor), Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase blood levels of atorvastatin.
Read the full Piperine + Ezetimibe, Atorvastatin interactionGrape Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
Read the full Grape Seed Extract + Ezetimibe, Atorvastatin interactionNiacinHepatotoxic Drugs, Hmg-coa Reductase Inhibitors ("statins") Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Ezetimibe, Atorvastatin interactionHigenamine HydrochlorideCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, higenamine might increase the levels and clinical effects drugs metabolized by CYP3A4.
Read the full Higenamine Hydrochloride + Ezetimibe, Atorvastatin interactionSynephrine HydrochlorideCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Bitter orange might increase levels of drugs metabolized by CYP3A4.
Read the full Synephrine Hydrochloride + Ezetimibe, Atorvastatin interactionVitamin E, PowderCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E, Powder + Ezetimibe, Atorvastatin interactionRhodiola RoseaCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, rhodiola might increase levels of drugs metabolized by CYP3A4.
Read the full Rhodiola Rosea + Ezetimibe, Atorvastatin interactionYohimbe ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, yohimbe might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Yohimbe Extract + Ezetimibe, Atorvastatin interactionHydrochlorothiazide, MethyldopaAldoril 15, Aldoril 25, Aldoril D30, Methazide
How Hydrochlorothiazide, Methyldopa interacts with Jacked & Sexy — through 10 ingredients. Tap an ingredient for the detail:
Mucuna PruriensMethyldopa (aldomet) Major
Interaction Summary
Theoretically, concomitant use of cowhage and methyldopa might increase the risk of hypotension.
Read the full Mucuna Pruriens + Hydrochlorothiazide, Methyldopa interactionOctopamine HydrochlorideAntihypertensive Drugs Moderate
Interaction Summary
In humans, octopamine 450-600 mg daily increases blood pressure in hypotensive patients.
Read the full Octopamine Hydrochloride + Hydrochlorothiazide, Methyldopa interactionN-isopropylnorsynephrine HclAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, isopropylnorsynephrine might decrease the effects of antihypertensive drugs.
Read the full N-isopropylnorsynephrine Hcl + Hydrochlorothiazide, Methyldopa interactionNiacinAntihypertensive Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
Read the full Niacin + Hydrochlorothiazide, Methyldopa interactionGreen TeaDiuretic Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, using green tea with diuretic drugs might increase the risk of hypokalemia.
Read the full Green Tea + Hydrochlorothiazide, Methyldopa interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Hydrochlorothiazide, Methyldopa interactionGuaranaDiuretic Drugs Moderate
Interaction Summary
Theoretically, using guarana with diuretic drugs might increase the risk of hypokalemia.
Read the full Guarana + Hydrochlorothiazide, Methyldopa interactionRhodiola RoseaAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking rhodiola with antihypertensive drugs might increase the risk of hypotension.
Read the full Rhodiola Rosea + Hydrochlorothiazide, Methyldopa interactionYohimbe ExtractAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, yohimbe might reduce the effects of antihypertensive drugs.
Read the full Yohimbe Extract + Hydrochlorothiazide, Methyldopa interactionN Methyl Tyramine HclAntihypertensive Drugs Minor
Interaction Summary
In animal research, N-methyltyramine increased blood pressure.
Read the full N Methyl Tyramine Hcl + Hydrochlorothiazide, Methyldopa interactionIsocarboxazidMarplan
How Isocarboxazid interacts with Jacked & Sexy — through 9 ingredients. Tap an ingredient for the detail:
Synephrine HydrochlorideMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, taking MAOIs with synephrine-containing bitter orange preparations might increase the hypertensive effects of synephrine, potentially leading to hypertensive crisis.
Read the full Synephrine Hydrochloride + Isocarboxazid interactionMucuna PruriensMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens + Isocarboxazid interactionYohimbe ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Concomitant use of MAOIs with yohimbe can result in additive effects.
Read the full Yohimbe Extract + Isocarboxazid interactionOctopamine HydrochlorideMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Octopamine is metabolized by monoamine oxidase.
Read the full Octopamine Hydrochloride + Isocarboxazid interactionGuaranaMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Read the full Guarana + Isocarboxazid interactionB-phenylethylamine HclSerotonergic Drugs, Monoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, combining serotonergic drugs with phenethylamine might increase the risk of serotonergic adverse effects.
Read the full B-phenylethylamine Hcl + Isocarboxazid interactionMethyl Hordenine HclMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Hordenine is structurally similar to tyramine In vitro research shows that hordenine is a selective substrate for monoamine oxidase-B in the liver.
Read the full Methyl Hordenine Hcl + Isocarboxazid interactionGreen TeaMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Read the full Green Tea + Isocarboxazid interactionRhodiola RoseaAntidepressant Drugs Minor
Interaction Summary
Theoretically, rhodiola might increase the risk of adverse effects when taken with antidepressants.
Read the full Rhodiola Rosea + Isocarboxazid interactionLevodopaInbrija, Larodopa
How Levodopa interacts with Jacked & Sexy — through 2 ingredients. Tap an ingredient for the detail:
Mucuna PruriensLevodopa Major
Interaction Summary
Concomitant use can increase the risk of levodopa-related adverse effects.
Read the full Mucuna Pruriens + Levodopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Levodopa interactionLevodopa, CarbidopaDuodopa
How Levodopa, Carbidopa interacts with Jacked & Sexy — through 2 ingredients. Tap an ingredient for the detail:
Mucuna PruriensLevodopa Major
Interaction Summary
Concomitant use can increase the risk of levodopa-related adverse effects.
Read the full Mucuna Pruriens + Levodopa, Carbidopa interactionVitamin B6Levodopa Minor
Interaction Summary
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Read the full Vitamin B6 + Levodopa, Carbidopa interactionMethyldopaAldomet, Methyldopa
How Methyldopa interacts with Jacked & Sexy — through 9 ingredients. Tap an ingredient for the detail:
Mucuna PruriensMethyldopa (aldomet) Major
Interaction Summary
Theoretically, concomitant use of cowhage and methyldopa might increase the risk of hypotension.
Read the full Mucuna Pruriens + Methyldopa interactionN-isopropylnorsynephrine HclAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, isopropylnorsynephrine might decrease the effects of antihypertensive drugs.
Read the full N-isopropylnorsynephrine Hcl + Methyldopa interactionOctopamine HydrochlorideAntihypertensive Drugs Moderate
Interaction Summary
In humans, octopamine 450-600 mg daily increases blood pressure in hypotensive patients.
Read the full Octopamine Hydrochloride + Methyldopa interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Methyldopa interactionGreen TeaHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea + Methyldopa interactionNiacinAntihypertensive Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
Read the full Niacin + Methyldopa interactionYohimbe ExtractAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, yohimbe might reduce the effects of antihypertensive drugs.
Read the full Yohimbe Extract + Methyldopa interactionRhodiola RoseaAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking rhodiola with antihypertensive drugs might increase the risk of hypotension.
Read the full Rhodiola Rosea + Methyldopa interactionN Methyl Tyramine HclAntihypertensive Drugs Minor
Interaction Summary
In animal research, N-methyltyramine increased blood pressure.
Read the full N Methyl Tyramine Hcl + Methyldopa interactionMidazolamNayzilam, Seizalam, Versed
How Midazolam interacts with Jacked & Sexy — through 10 ingredients. Tap an ingredient for the detail:
Synephrine HydrochlorideCytochrome P450 3a4 (cyp3a4) Substrates, Midazolam (versed) Major
Interaction Summary
Bitter orange might increase levels of drugs metabolized by CYP3A4.
Read the full Synephrine Hydrochloride + Midazolam interactionHigenamine HydrochlorideCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, higenamine might increase the levels and clinical effects drugs metabolized by CYP3A4.
Read the full Higenamine Hydrochloride + Midazolam interactionMucuna PruriensAnesthesia Moderate
Interaction Summary
Theoretically, concomitant use of cowhage and anesthesia might increase the risk of arrhythmias.
Read the full Mucuna Pruriens + Midazolam interactionGrape Seed ExtractMidazolam (versed), Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, long-term intake of grape seed extract might decrease the effects of midazolam.
Read the full Grape Seed Extract + Midazolam interactionTheacrineCns Depressants Moderate
Interaction Summary
Theoretically, theacrine might alter the effects of CNS depressants.
Read the full Theacrine + Midazolam interactionPiperineCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Piperine + Midazolam interactionVitamin E, PowderCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Read the full Vitamin E, Powder + Midazolam interactionRhodiola RoseaCytochrome P450 3a4 (cyp3a4) Substrates, Cns Depressants Minor
Interaction Summary
Theoretically, rhodiola might increase levels of drugs metabolized by CYP3A4.
Read the full Rhodiola Rosea + Midazolam interactionGreen TeaCytochrome P450 3a4 (cyp3a4) Substrates, Midazolam (versed) Minor
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea + Midazolam interactionYohimbe ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, yohimbe might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Yohimbe Extract + Midazolam interactionMoclobemideManerix, Moclobemide
How Moclobemide interacts with Jacked & Sexy — through 9 ingredients. Tap an ingredient for the detail:
Yohimbe ExtractCytochrome P450 2d6 (cyp2d6) Inhibitors, Monoamine Oxidase Inhibitors (maois) Major
Interaction Summary
CYP2D6 inhibitors may increase the levels and adverse effects of yohimbine, a constituent of yohimbe.
Read the full Yohimbe Extract + Moclobemide interactionSynephrine HydrochlorideMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, taking MAOIs with synephrine-containing bitter orange preparations might increase the hypertensive effects of synephrine, potentially leading to hypertensive crisis.
Read the full Synephrine Hydrochloride + Moclobemide interactionMucuna PruriensMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens + Moclobemide interactionGreen TeaMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Read the full Green Tea + Moclobemide interactionGuaranaMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Read the full Guarana + Moclobemide interactionOctopamine HydrochlorideMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Octopamine is metabolized by monoamine oxidase.
Read the full Octopamine Hydrochloride + Moclobemide interactionMethyl Hordenine HclMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Hordenine is structurally similar to tyramine In vitro research shows that hordenine is a selective substrate for monoamine oxidase-B in the liver.
Read the full Methyl Hordenine Hcl + Moclobemide interactionB-phenylethylamine HclMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, taking phenethylamine concomitantly with MAOIs may increase adverse effects.
Read the full B-phenylethylamine Hcl + Moclobemide interactionRhodiola RoseaAntidepressant Drugs Minor
Interaction Summary
Theoretically, rhodiola might increase the risk of adverse effects when taken with antidepressants.
Read the full Rhodiola Rosea + Moclobemide interactionNadololCorgard, Nadolol
How Nadolol interacts with Jacked & Sexy — through 8 ingredients. Tap an ingredient for the detail:
Green TeaNadolol (corgard) Major
Interaction Summary
Green tea seems to reduce the levels and clinical effects of nadolol.
Read the full Green Tea + Nadolol interactionN-isopropylnorsynephrine HclAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, isopropylnorsynephrine might decrease the effects of antihypertensive drugs.
Read the full N-isopropylnorsynephrine Hcl + Nadolol interactionOctopamine HydrochlorideAntihypertensive Drugs Moderate
Interaction Summary
In humans, octopamine 450-600 mg daily increases blood pressure in hypotensive patients.
Read the full Octopamine Hydrochloride + Nadolol interactionRhodiola RoseaAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking rhodiola with antihypertensive drugs might increase the risk of hypotension.
Read the full Rhodiola Rosea + Nadolol interactionYohimbe ExtractAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, yohimbe might reduce the effects of antihypertensive drugs.
Read the full Yohimbe Extract + Nadolol interactionNiacinAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
Read the full Niacin + Nadolol interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Nadolol interactionN Methyl Tyramine HclAntihypertensive Drugs Minor
Interaction Summary
In animal research, N-methyltyramine increased blood pressure.
Read the full N Methyl Tyramine Hcl + Nadolol interactionOzanimod HydrochlorideZeposia
How Ozanimod Hydrochloride interacts with Jacked & Sexy — through 11 ingredients. Tap an ingredient for the detail:
Synephrine HydrochlorideQt Interval-prolonging Drugs, Monoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, bitter orange might have an additive effect when combined with drugs that prolong the QT interval, potentially increasing the risk of ventricular arrhythmias.
Read the full Synephrine Hydrochloride + Ozanimod Hydrochloride interactionMucuna PruriensMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens + Ozanimod Hydrochloride interactionYohimbe ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Concomitant use of MAOIs with yohimbe can result in additive effects.
Read the full Yohimbe Extract + Ozanimod Hydrochloride interactionRhodiola RoseaImmunosuppressants Moderate
Interaction Summary
Theoretically, rhodiola use might interfere with immunosuppressive therapy.
Read the full Rhodiola Rosea + Ozanimod Hydrochloride interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Ozanimod Hydrochloride interactionGreen TeaMonoamine Oxidase Inhibitors (maois), Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Read the full Green Tea + Ozanimod Hydrochloride interactionGuaranaMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Read the full Guarana + Ozanimod Hydrochloride interactionAdaptogen MaxImmunosuppressants Moderate
Interaction Summary
Theoretically, jiaogulan might decrease the effectiveness of immunosuppressive therapy.
Read the full Adaptogen Max + Ozanimod Hydrochloride interactionB-phenylethylamine HclMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, taking phenethylamine concomitantly with MAOIs may increase adverse effects.
Read the full B-phenylethylamine Hcl + Ozanimod Hydrochloride interactionMethyl Hordenine HclMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Hordenine is structurally similar to tyramine In vitro research shows that hordenine is a selective substrate for monoamine oxidase-B in the liver.
Read the full Methyl Hordenine Hcl + Ozanimod Hydrochloride interactionOctopamine HydrochlorideMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Octopamine is metabolized by monoamine oxidase.
Read the full Octopamine Hydrochloride + Ozanimod Hydrochloride interactionPhenelzine SulfateNardil
How Phenelzine Sulfate interacts with Jacked & Sexy — through 10 ingredients. Tap an ingredient for the detail:
Yohimbe ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Concomitant use of MAOIs with yohimbe can result in additive effects.
Read the full Yohimbe Extract + Phenelzine Sulfate interactionSynephrine HydrochlorideMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, taking MAOIs with synephrine-containing bitter orange preparations might increase the hypertensive effects of synephrine, potentially leading to hypertensive crisis.
Read the full Synephrine Hydrochloride + Phenelzine Sulfate interactionMucuna PruriensMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens + Phenelzine Sulfate interactionB-phenylethylamine HclMonoamine Oxidase Inhibitors (maois), Serotonergic Drugs Moderate
Interaction Summary
Theoretically, taking phenethylamine concomitantly with MAOIs may increase adverse effects.
Read the full B-phenylethylamine Hcl + Phenelzine Sulfate interactionTheacrineCns Depressants Moderate
Interaction Summary
Theoretically, theacrine might alter the effects of CNS depressants.
Read the full Theacrine + Phenelzine Sulfate interactionMethyl Hordenine HclMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Hordenine is structurally similar to tyramine In vitro research shows that hordenine is a selective substrate for monoamine oxidase-B in the liver.
Read the full Methyl Hordenine Hcl + Phenelzine Sulfate interactionGuaranaMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Read the full Guarana + Phenelzine Sulfate interactionGreen TeaMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Read the full Green Tea + Phenelzine Sulfate interactionOctopamine HydrochlorideMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Octopamine is metabolized by monoamine oxidase.
Read the full Octopamine Hydrochloride + Phenelzine Sulfate interactionRhodiola RoseaCns Depressants, Antidepressant Drugs Minor
Interaction Summary
Theoretically, rhodiola might increase the risk of adverse effects when taken with CNS depressants.
Read the full Rhodiola Rosea + Phenelzine Sulfate interactionRasagilineAzilect
How Rasagiline interacts with Jacked & Sexy — through 11 ingredients. Tap an ingredient for the detail:
Yohimbe ExtractMonoamine Oxidase Inhibitors (maois), Cytochrome P450 1a2 (cyp1a2) Substrates Major
Interaction Summary
Concomitant use of MAOIs with yohimbe can result in additive effects.
Read the full Yohimbe Extract + Rasagiline interactionMucuna PruriensMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens + Rasagiline interactionSynephrine HydrochlorideMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, taking MAOIs with synephrine-containing bitter orange preparations might increase the hypertensive effects of synephrine, potentially leading to hypertensive crisis.
Read the full Synephrine Hydrochloride + Rasagiline interactionGrape Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, grape juice might reduce the levels of CYP1A2 substrates.
Read the full Grape Seed Extract + Rasagiline interactionGreen TeaMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Read the full Green Tea + Rasagiline interactionGuaranaMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Read the full Guarana + Rasagiline interactionB-phenylethylamine HclSerotonergic Drugs, Monoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, combining serotonergic drugs with phenethylamine might increase the risk of serotonergic adverse effects.
Read the full B-phenylethylamine Hcl + Rasagiline interactionMethyl Hordenine HclMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Hordenine is structurally similar to tyramine In vitro research shows that hordenine is a selective substrate for monoamine oxidase-B in the liver.
Read the full Methyl Hordenine Hcl + Rasagiline interactionOctopamine HydrochlorideMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Octopamine is metabolized by monoamine oxidase.
Read the full Octopamine Hydrochloride + Rasagiline interactionPiperineCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Piperine + Rasagiline interactionRhodiola RoseaCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rhodiola might increase levels of drugs metabolized by CYP1A2.
Read the full Rhodiola Rosea + Rasagiline interactionSafinamide MesylateXadago
How Safinamide Mesylate interacts with Jacked & Sexy — through 8 ingredients. Tap an ingredient for the detail:
Yohimbe ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Concomitant use of MAOIs with yohimbe can result in additive effects.
Read the full Yohimbe Extract + Safinamide Mesylate interactionMucuna PruriensMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens + Safinamide Mesylate interactionSynephrine HydrochlorideMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, taking MAOIs with synephrine-containing bitter orange preparations might increase the hypertensive effects of synephrine, potentially leading to hypertensive crisis.
Read the full Synephrine Hydrochloride + Safinamide Mesylate interactionOctopamine HydrochlorideMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Octopamine is metabolized by monoamine oxidase.
Read the full Octopamine Hydrochloride + Safinamide Mesylate interactionGreen TeaMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Read the full Green Tea + Safinamide Mesylate interactionGuaranaMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Read the full Guarana + Safinamide Mesylate interactionMethyl Hordenine HclMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Hordenine is structurally similar to tyramine In vitro research shows that hordenine is a selective substrate for monoamine oxidase-B in the liver.
Read the full Methyl Hordenine Hcl + Safinamide Mesylate interactionB-phenylethylamine HclSerotonergic Drugs, Monoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, combining serotonergic drugs with phenethylamine might increase the risk of serotonergic adverse effects.
Read the full B-phenylethylamine Hcl + Safinamide Mesylate interactionSelegilineCarbex, Eldepryl, Emsam, Zelapar
How Selegiline interacts with Jacked & Sexy — through 9 ingredients. Tap an ingredient for the detail:
Mucuna PruriensMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, concomitant use of cowhage and non-selective MAOIs might increase the risk of hypertensive crisis.
Read the full Mucuna Pruriens + Selegiline interactionSynephrine HydrochlorideMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Theoretically, taking MAOIs with synephrine-containing bitter orange preparations might increase the hypertensive effects of synephrine, potentially leading to hypertensive crisis.
Read the full Synephrine Hydrochloride + Selegiline interactionYohimbe ExtractMonoamine Oxidase Inhibitors (maois) Major
Interaction Summary
Concomitant use of MAOIs with yohimbe can result in additive effects.
Read the full Yohimbe Extract + Selegiline interactionGreen TeaMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Read the full Green Tea + Selegiline interactionB-phenylethylamine HclSerotonergic Drugs, Monoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, combining serotonergic drugs with phenethylamine might increase the risk of serotonergic adverse effects.
Read the full B-phenylethylamine Hcl + Selegiline interactionMethyl Hordenine HclMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Hordenine is structurally similar to tyramine In vitro research shows that hordenine is a selective substrate for monoamine oxidase-B in the liver.
Read the full Methyl Hordenine Hcl + Selegiline interactionGuaranaMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Read the full Guarana + Selegiline interactionOctopamine HydrochlorideMonoamine Oxidase Inhibitors (maois) Moderate
Interaction Summary
Octopamine is metabolized by monoamine oxidase.
Read the full Octopamine Hydrochloride + Selegiline interactionRhodiola RoseaAntidepressant Drugs Minor
Interaction Summary
Theoretically, rhodiola might increase the risk of adverse effects when taken with antidepressants.
Read the full Rhodiola Rosea + Selegiline interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Jacked & Sexy with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Green Tea
Atorvastatin (Lipitor)
Green tea extract seems to reduce the levels and clinical effects of atorvastatin.
In healthy humans, taking green tea extract 300 mg or 600 mg along with atorvastatin reduces plasma levels of atorvastatin by approximately 24%. The elimination of atorvastatin is not affected. Atorvastatin is a substrate of organic anion-transporting polypeptides (OATPs). Research shows that two of the major catechins found in green tea, epicatechin gallate (ECG) and epigallocatechin gallate (EGCG), inhibit OATPs. Some OATPs are expressed in the small intestine and are responsible for the uptake of drugs and other compounds, which may have resulted in reduced plasma levels of atorvastatin. It is not clear if drinking green tea alters the absorption of atorvastatin.
Ephedrine
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Green tea contains caffeine. There is evidence that using ephedrine with caffeine might increase the risk of serious life-threatening or debilitating adverse effects such as hypertension, myocardial infarction, stroke, seizures, and death.
Nadolol (Corgard)
Green tea seems to reduce the levels and clinical effects of nadolol.
Preliminary clinical research shows that green tea consumption reduces plasma concentrations of nadolol. Compared to a control group, both peak levels and total drug exposure (AUC) of nadolol were reduced by approximately 85% in subjects who drank green tea daily for two weeks. Drinking green tea with nadolol also significantly reduced nadolol's systolic blood pressure lowering effect. Other clinical research shows that a single dose of green tea can affect plasma nadolol levels for at least one hour. Green tea catechins have been shown to inhibit organic anion transporting polypeptides (OATP), one of which, OATP1A2, is involved in the uptake of nadolol in the intestine The interaction is thought to be due primarily to the epigallocatechin gallate (EGCG) content of green tea.
5-Fluorouracil
Theoretically, high doses of green tea might increase the effects and side effects of 5-fluorouracil.
Animal research shows that taking green tea in amounts equivalent to about 6 cups daily in humans for 4 weeks prior to receiving a single injection of 5-fluorouracil increases the maximum plasma levels of 5-fluorouracil by about 2.5-fold and the area under the curve by 425%.
Adenosine (Adenocard)
Theoretically, green tea might decrease the vasodilatory effects of adenosine and interfere with its use prior to stress testing.
Green tea contains caffeine. Caffeine is a competitive inhibitor of adenosine at the cellular level. However, caffeine doesn't seem to affect supplemental adenosine because high interstitial levels of adenosine overcome the antagonistic effects of caffeine. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. However, methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Anticoagulant/Antiplatelet Drugs
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Conflicting reports exist regarding the effect of green tea on bleeding risk when used with anticoagulant or antiplatelet drugs; however, most evidence suggests that drinking green tea in moderate amounts is unlikely to cause a significant interaction. Green tea contains small amounts of vitamin K, approximately 7 mcg per cup. Some case reports have associated the antagonism of warfarin with the vitamin K content of green tea. However, these reports are rare, and very large doses of green tea (about 8-16 cups daily) appear to be needed to cause these effects. Furthermore, the catechins and caffeine in green tea are reported to have antiplatelet activity.
Beta-Adrenergic Agonists
Green tea contains caffeine. Theoretically, concomitant use of large amounts of caffeine might increase cardiac inotropic effects of beta-agonists.
Bortezomib (Velcade)
Theoretically, green tea might interfere with the effects of bortezomib.
In vitro research shows that green tea polyphenols, such as epigallocatechin gallate (EGCG), interact with bortezomib and block its proteasome inhibitory action. This prevents the induction of cell death in multiple myeloma or glioblastoma cancer cell lines. Advise patients taking bortezomib, not to take green tea.
Carbamazepine (Tegretol)
Theoretically, green tea might reduce the effects of carbamazepine and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that taking caffeine can lower the anticonvulsant effects of carbamazepine and can induce seizures when taken in doses above 400 mg/kg. Human research has shown that taking caffeine 300 mg in three divided doses along with carbamazepine 200 mg reduces the bioavailability of carbamazepine by 32% and prolongs the plasma half-life of carbamazepine 2-fold in healthy individuals.
Celiprolol (Celicard)
Theoretically, green tea might reduce the levels and clinical effects of celiprolol.
In a small human study, taking green tea daily for 4 days appears to decrease blood and urine levels of celiprolol by at least 98%. This interaction is possibly due to the inhibition of organic anion transporting polypeptide (OATP). Green tea catechins have been shown to inhibit organic anion transporting polypeptides (OATP), one of which, OATP1A2, is found in the intestine The interaction is thought to be due primarily to the epigallocatechin gallate (EGCG) content of green tea.
Cimetidine (Tagamet)
Theoretically, concomitant use might increase the effects and adverse effects of caffeine in green tea.
Green tea contains caffeine. Cimetidine can reduce caffeine clearance by 31% to 42%.
Clozapine (Clozaril)
Theoretically, green tea might increase the levels and adverse effects of clozapine and acutely exacerbate psychotic symptoms.
Animal research suggests that, although green tea extract does not affect the elimination of clozapine, it delays the time to reach peak concentration and reduces the peak plasma levels. Also, concomitant administration of green tea and clozapine might theoretically cause acute exacerbation of psychotic symptoms due to the caffeine in green tea. Caffeine can increase the effects and toxicity of clozapine. Caffeine doses of 400-1000 mg daily inhibit clozapine metabolism. Clozapine is metabolized by cytochrome P450 1A2 (CYP1A2). Researchers speculate that caffeine might inhibit CYP1A2. However, there is no reliable evidence that caffeine affects CYP1A2. There is also speculation that genetic factors might make some patients be more sensitive to the interaction between clozapine and caffeine.
Contraceptive Drugs
Theoretically, concomitant use might increase the effects and adverse effects of caffeine found in green tea.
Green tea contains caffeine. Oral contraceptives can decrease caffeine clearance by 40% to 65%.
Cytochrome P450 1A2 (Cyp1A2) Inhibitors
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Caffeine is metabolized by cytochrome P450 1A2 (CYP1A2),. Theoretically, drugs that inhibit CYP1A2 may decrease the clearance rate of caffeine from green tea and increase caffeine levels.
Dipyridamole (Persantine)
Theoretically, green tea might decrease the vasodilatory effects of dipyridamole and interfere with its use prior to stress testing.
Green tea contains caffeine. Caffeine might inhibit dipyridamole-induced vasodilation. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. Methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Disulfiram (Antabuse)
Theoretically, disulfiram might increase the risk of adverse effects from caffeine.
In human research, disulfiram decreases the clearance and increases the half-life of caffeine.
Diuretic Drugs
Theoretically, using green tea with diuretic drugs might increase the risk of hypokalemia.
Green tea contains caffeine. In excessive amounts, caffeine can reduce potassium levels due to stimulation of the sodium-potassium pump. Diuretics can also cause lower potassium levels.
Estrogens
Theoretically, estrogens might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Estrogen inhibits caffeine metabolism.
Ethosuximide (Zarontin)
Theoretically, green tea might reduce the effects of ethosuximide and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that caffeine 92.4 mg/kg can decrease the anticonvulsant activity of ethosuximide. However, this effect has not been reported in humans.
Felbamate (Felbatol)
Theoretically, green tea might reduce the effects of felbamate and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that a high dose of caffeine 161.7 mg/kg can decreases the anticonvulsant activity of felbamate. However, this effect has not been reported in humans.
Fexofenadine (Allegra)
Green tea can decrease blood levels of fexofenadine.
Clinical research shows that green tea can significantly decrease blood levels and excretion of fexofenadine. Taking green tea extract with a dose of fexofenadine decreased bioavailability of fexofenadine by about 30%. In vitro, green tea inhibits the cellular accumulation of fexofenadine by inhibiting the organic anion transporting polypeptide (OATP) drug transporter. Research shows that two of the major catechins found in green tea, epicatechin gallate (ECG) and epigallocatechin gallate (EGCG), inhibit OATPs, specifically OATP1A2, OATP1B1, and OATP2B1. In addition, green tea has been shown to reduce the absorption of some drugs that are OATP substrates.
Flutamide (Eulexin)
Theoretically, green tea might increase the levels and adverse effects of flutamide.
Green tea contains caffeine. In vitro evidence suggests that caffeine can inhibit the metabolism of flutamide. Theoretically, concomitant use of caffeine and flutamide might increase serum concentrations of flutamide and increase the risk adverse effects.
Fluvoxamine (Luvox)
Theoretically, fluvoxamine might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Fluvoxamine reduces caffeine metabolism.
Hepatotoxic Drugs
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Green tea extract supplements have been linked to several cases of hepatotoxicity and might have additive hepatotoxic effects with other drugs..
Imatinib (Gleevec)
Theoretically, green tea might reduce the levels and clinical effects of imatinib.
In animal research, a single dose of green tea extract reduces the area under the curve (AUC) of imatinib by up to approximately 64% and its main metabolite N-desmethyl imatinib by up to approximately 81%. This interaction has not been shown in humans. The mechanism of action is unclear but may involve multiple pathways.
Yohimbine Hydrochloride
Monoamine Oxidase Inhibitors (Maois)
Concomitant use of MAOIs with yohimbe can result in additive effects.
Yohimbine, a constituent of yohimbe, has MAO inhibitory effects. At high doses, yohimbine is a non-selective inhibitor of MAO.
Antihypertensive Drugs
Theoretically, yohimbe might reduce the effects of antihypertensive drugs.
Yohimbine, a constituent of yohimbe, is an alpha-2 adrenoceptor antagonist and has been reported to increase blood pressure in clinical research. Theoretically, concomitant use of yohimbe and antihypertensive drugs can interfere with blood pressure control.
Clonidine (Catapres)
Theoretically, yohimbe might precipitate clonidine withdrawal.
Chronic clonidine use can downregulate alpha-2 adrenoreceptors. Animal research and one human case report suggest that concomitant administration of yohimbine, an alpha-2 adrenoceptor antagonist, may precipitate clonidine withdrawal and lead to sympathomimetic toxicity, including hypertensive crisis.
Cytochrome P450 2D6 (Cyp2D6) Inhibitors
CYP2D6 inhibitors may increase the levels and adverse effects of yohimbine, a constituent of yohimbe.
In vitro and clinical research shows that the yohimbe bark constituent, yohimbine, is metabolized by CYP2D6 isoenzymes. Paroxetine, a cytochrome P450 (CYP) 2D6 inhibitor, increases the maximum serum concentration of yohimbine and reduces the clearance of yohimbine compared to yohimbine alone in patients who are extensive CYP2D6 metabolizers..
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, yohimbe might increase the levels and adverse effects of CYP2D6 substrates.
In vitro research suggests that yohimbine, a constituent of yohimbe bark, inhibits CYP2D6 enzyme activity.
Cytochrome P450 3A4 (Cyp3A4) Inhibitors
Theoretically, CYP3A4 inhibitors might increase the levels and adverse effects of yohimbine, a constituent of yohimbe bark.
In vitro and clinical research shows that the yohimbe bark constituent, yohimbine, is metabolized by CYP3A4 enzymes. Theoretically, drugs that inhibit CYP3A4 might increase the levels and adverse effects of yohimbine.
Paroxetine (Paxil)
Paroxetine decreases the clearance of yohimbine and may increase its effects.
Paroxetine, a cytochrome P450 (CYP) 2D6 inhibitor, increases the maximum serum concentration of yohimbine by about 350% and reduces the clearance of yohimbine by about 80% compared to yohimbine alone in patients who are extensive CYP2D6 metabolizers. No significant changes in pharmacokinetic parameters of yohimbine were observed with coadministration of paroxetine in patients who are poor CYP2D6 metabolizers.
Phenothiazines
Theoretically, using yohimbine with phenothiazines might have additive effects.
Yohimbine, a constituent of yohimbe, has alpha-2 adrenergic antagonist effects. Theoretically, combining it with phenothiazines can cause additive alpha-2 adrenergic antagonism.
Stimulant Drugs
Theoretically, taking yohimbe with stimulant drugs can have additive effects.
Yohimbine, a constituent of yohimbe, has sympathomimetic effects and increases blood pressure in a dose-dependent manner. Theoretically, taking yohimbe with stimulant drugs can have additive stimulant and hypertensive effects.
Tricyclic Antidepressants (Tcas)
Theoretically, taking yohimbe with TCAs can increase adverse effects.
A small clinical study in patients taking TCAs for at least 4 weeks shows that receiving doses of intravenous yohimbine 2.5-20 mg daily for up to 7 days precipitates severe anxiety, agitation, and tremor. The effects of yohimbe bark itself are unclear; oral yohimbe bark contains 0.6% to 1.38% yohimbine, but it is unclear how much is absorbed.
Anticoagulant/Antiplatelet Drugs
Theoretically, combining yohimbe bark with antiplatelet or anticoagulant drugs might have additive effects; however, this has not been reported in clinical research.
Research in healthy adults shows that taking yohimbine, a constituent of yohimbe bark, in doses of 8 mg or more, seems to inhibit platelet aggregation in vitro by binding to the alpha-2 adrenoceptor. The effects of yohimbe bark itself are unclear; yohimbe bark contains 0.6% to 1.38% yohimbine, but it is unclear how much is absorbed.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, yohimbe might decrease the levels and clinical effects of CYP1A2 substrates.
In vitro research shows that yohimbe extract induces CYP1A2 enzymes.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, yohimbe might decrease the levels and clinical effects of CYP3A4 substrates.
In vitro research shows that yohimbe extract induces CYP3A4 enzymes.
Piperine
Anticoagulant/Antiplatelet Drugs
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
In vitro research shows that piperine, a constituent of black pepper, seems to inhibit platelet aggregation. This has not been reported in humans.
Antidiabetes Drugs
Theoretically, black pepper might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Animal research shows that piperine, a constituent of black pepper, can reduce blood glucose levels. Monitor blood glucose levels closely. Dose adjustments might be necessary.
Atorvastatin (Lipitor)
Theoretically, black pepper might increase blood levels of atorvastatin.
Animal research shows that taking piperine, a constituent of black pepper, 35 mg/kg can increase the maximum serum concentration of atorvastatin three-fold. This has not been reported in humans.
Cyclosporine (Neoral, Sandimmune)
Theoretically, black pepper might increase the effects and side effects of cyclosporine.
In vitro research shows that piperine, a constituent of black pepper, increases the bioavailability of cyclosporine. This has not been reported in humans.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
In vitro research suggests that some constituents of black pepper inhibit CYP2D6. This has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
In vitro research and pharmacokinetic simulation data suggest that piperine, a constituent of black pepper, as well as the pepper fruit seem to inhibit CYP3A4. This has not been reported in humans.
Lithium
Theoretically, black pepper might increase blood levels of lithium due to its diuretic effects. The dose of lithium might need to be reduced.
Black pepper is thought to have diuretic properties.
Nevirapine (Viramune)
Black pepper might increase blood levels of nevirapine.
Clinical research shows that piperine, a constituent of black pepper, increases the plasma concentration of nevirapine. However, no adverse effects were observed in this study.
P-Glycoprotein Substrates
Theoretically, black pepper might increase levels of P-glycoprotein substrates.
In vitro research shows that piperine, a constituent of black pepper, seems to inhibit P-glycoprotein.
Pentobarbital (Nembutal)
Theoretically, black pepper might increase the sedative effects of pentobarbital.
Animal research shows that piperine, a constituent of black pepper, increases pentobarbital-induced sleeping time.
Phenytoin (Dilantin)
Black pepper might increase blood levels of phenytoin.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption, slow elimination, and increase levels of phenytoin. Taking a single dose of black pepper 1 gram along with phenytoin seems to double the serum concentration of phenytoin. Consuming a soup with black pepper providing piperine 44 mg/200 mL of soup along with phenytoin also seems to increase phenytoin levels when compared with consuming the same soup without black pepper.
Propranolol (Inderal)
Black pepper might increase blood levels of propranolol.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and slow elimination of propranolol.
Rifampin (Rifadin)
Black pepper might increase blood levels of rifampin.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and serum levels of rifampin.
Theophylline
Black pepper might increase blood levels of theophylline.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and slow elimination of theophylline.
Amoxicillin (Amoxil, Trimox)
Theoretically, black pepper might increase the effects and side effects of amoxicillin.
Animal research shows that taking piperine, a constituent of black pepper, with amoxicillin increases plasma levels of amoxicillin. This has not been reported in humans.
Carbamazepine (Tegretol)
Theoretically, black pepper might increase blood levels of carbamazepine, potentially increasing the effects and side effects of carbamazepine.
One clinical study in patients taking carbamazepine 300 mg or 500 mg twice daily shows that taking a single 20 mg dose of purified piperine, a constituent of black pepper, increases carbamazepine levels. Piperine may increase carbamazepine absorption by increasing blood flow to the GI tract, increasing the surface area of the small intestine, or inhibiting cytochrome P450 3A4 (CYP3A4) in the gut wall. Absorption was significantly increased by 7-10 mcg/mL/hour. The time to eliminate carbamazepine was also increased by 4-8 hours. Although carbamazepine levels were increased, this did not appear to increase side effects. In vitro research also shows that piperine can increase carbamazepine levels by 11% in a time-dependent manner.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
In vitro research suggests that black pepper induces CYP1A2. This has not been reported in humans.
Synephrine Hydrochloride
Midazolam (Versed)
Bitter orange might increase blood levels of midazolam.
One small clinical study shows that bitter orange juice can increase midazolam levels, likely through inhibition of cytochrome P450 3A4 (CYP3A4). Theoretically, bitter orange might increase the risk of midazolam-related adverse effects.
Monoamine Oxidase Inhibitors (Maois)
Theoretically, taking MAOIs with synephrine-containing bitter orange preparations might increase the hypertensive effects of synephrine, potentially leading to hypertensive crisis.
Bitter orange contains tyramine, octopamine, and synephrine, which are MAO substrates.
Antidiabetes Drugs
Theoretically, bitter orange might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Some clinical research shows that drinking a tea containing bitter orange and Indian snakeroot reduces fasting and postprandial glucose levels in patients with type 2 diabetes who are using antidiabetes drugs. However, it is unclear if these effects are due to bitter orange, Indian snakeroot, or the combination. An animal study also shows that p-synephrine in combination with gliclazide , a sulfonylurea, causes an additional 20% to 44% decrease in glucose levels when compared with gliclazide alone.
Caffeine
Bitter orange might increase blood pressure and heart rate when taken with caffeine.
Small clinical studies show that taking bitter orange in combination with caffeine can increase blood pressure and heart rate in otherwise healthy normotensive adults. Theoretically, this might increase the risk of serious cardiovascular adverse effects.
Colchicine
Bitter orange might affect colchicine levels.
Colchicine is a substrate of P-glycoprotein and cytochrome P450 3A4 (CYP3A4). Bitter orange has been reported to inhibit CYP3A4 and increase levels of CYP3A4 substrates. However, one small clinical study in healthy adults shows that drinking bitter orange juice 240 mL twice daily for 4 days and taking a single dose of colchicine 0.6 mg on the 4th day decreases colchicine peak serum levels by 24%, time to peak serum level by 1 hour, and overall exposure to colchicine by 20%. The clinical significance of this finding is unclear.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Bitter orange might increase levels of drugs metabolized by CYP3A4.
Small clinical studies suggest that single or multiple doses of freshly squeezed bitter orange juice 200-240 mL can inhibit CYP3A4 metabolism of drugs, causing increased drug levels and potentially increasing the risk of adverse effects. However, the extent of the effect of bitter orange on CYP3A4-mediated drug interactions is unknown. Some evidence suggests that bitter orange selectively inhibits intestinal CYP3A4, but not hepatic CYP3A4. Its effect on P-glycoprotein, which strongly overlaps with CYP3A4 interactions, is unclear. One small clinical study shows that drinking 8 ounces of freshly squeezed bitter orange juice has no effect on cyclosporine, which seems to be more dependent on hepatic CYP3A4 and P-glycoprotein than intestinal CYP3A4.
Dextromethorphan (Robitussin Dm, Others)
Bitter orange might increase blood levels of dextromethorphan.
One small clinical study shows that bitter orange juice increases dextromethorphan levels, likely through cytochrome P450 3A4 (CYP3A4) inhibition. Theoretically, bitter orange might increase the risk for dextromethorphan-related adverse effects.
Felodipine (Plendil)
Bitter orange might increase blood levels of felodipine.
One small clinical study shows that bitter orange juice increases felodipine levels, likely through cytochrome P450 3A4 (CYP3A4) inhibition. Theoretically, bitter orange might increase the risk for felodipine-related adverse effects.
Indinavir (Crixivan)
Bitter orange might increase blood levels of indinavir.
One small clinical study shows that bitter orange juice slightly increases indinavir levels, but this effect is likely to be clinically insignificant. Bitter orange selectively inhibits intestinal cytochrome P450 3A4 (CYP3A4); however, the metabolism of indinavir seems to be more dependent on hepatic CYP3A4. The effect of bitter orange on other protease inhibitors has not been studied.
Qt Interval-Prolonging Drugs
Theoretically, bitter orange might have an additive effect when combined with drugs that prolong the QT interval, potentially increasing the risk of ventricular arrhythmias.
One case report suggests that taking bitter orange in combination with other stimulants such as caffeine might prolong the QT interval in some patients.
Sildenafil (Viagra)
Bitter orange juice might increase blood levels of sildenafil.
A small clinical study in healthy adult males shows that drinking freshly squeezed bitter orange juice 250 mL daily for 3 days and taking a single dose of sildenafil 50 mg on the 3rd day increases the peak plasma concentration of sildenafil by 18% and the overall exposure to sildenafil by 44%. Theoretically, this may be due to inhibition of cytochrome P450 3A4 by bitter orange.
Stimulant Drugs
Theoretically, bitter orange might increase the risk of hypertension and adverse cardiovascular effects when taken with stimulant drugs.
Bitter orange appears to have stimulant effects.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, bitter orange might increase levels of drug metabolized by CYP2D6.
In vitro research shows that octopamine, a constituent of bitter orange, weakly inhibits CYP2D6 enzymes. This effect has not been reported in humans.
Grape seed extract
Anticoagulant/Antiplatelet Drugs
Theoretically, grape extracts may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro evidence suggests that grape extracts might decrease platelet aggregation.
Cyclosporine (Neoral, Sandimmune)
Ingesting grape juice with cyclosporine can reduce cyclosporine absorption.
A small pharmacokinetic study in healthy young adults shows that intake of purple grape juice 200 mL along with cyclosporine can decrease the absorption of cyclosporine by up to 30% when compared with water. Separate doses of grape juice and cyclosporine by at least 2 hours to avoid this interaction.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, grape juice might reduce the levels of CYP1A2 substrates.
A small pharmacokinetic study in healthy adults shows that ingestion of 200 mL of grape juice decreases phenacetin plasma levels. This is thought to be due to induction of CYP1A2.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, grape seed extract may increase the levels of CYP2D6 substrates.
In vitro evidence suggests that grape seed extract might inhibit CYP2D6 enzymes. However, this interaction has not been reported in humans.
Cytochrome P450 2E1 (Cyp2E1) Substrates
Theoretically, grape seed extract might increase the levels of CYP2E1 substrates.
In vitro and animal research suggests that grape seed proanthocyanidin extract inhibits CYP2E1 enzymes. However, this interaction has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
In vitro evidence suggests that grape seed extract might inhibit CYP3A4 enzymes. However, evidence from animal research shows that grape seed extract may induce CYP3A4 in the liver. So far, these interactions have not been reported in humans.
Midazolam (Versed)
Theoretically, long-term intake of grape seed extract might decrease the effects of midazolam.
Animal research shows that subchronic ingestions of grape seed extract can increase the elimination of intravenous midazolam by increasing hepatic CYP3A4 activity. Single doses of grape seed extract do not appear to affect midazolam elimination.
Phenacetin
Grape juice might decrease phenacetin absorption.
A small pharmacokinetic study in healthy adults shows that ingestion of 200 mL of grape juice decreases phenacetin plasma levels. This is thought to be due to induction of cytochrome P450 1A2 (CYP1A2).
Cytochrome P450 2C9 (Cyp2C9) Substrates
It is unclear if grape juice or grape seed extract inhibits CYP2C9; research is conflicting.
In vitro evidence shows that grape seed extract or grape juice might inhibit CYP2C9 enzymes. However, a small pharmacokinetic study in healthy adults shows that drinking 8 ounces of grape juice once does not affect the clearance of flurbiprofen, a probe-drug for CYP2C9 metabolism. The effects of continued grape juice consumption are unclear.
Higenamine Hydrochloride
Anticoagulant/Antiplatelet Drugs
Theoretically, higenamine might increase the risk of bleeding or bruising when taken with anticoagulant/antiplatelet drugs.
Animal research shows that higenamine inhibits platelet aggregation and reduces the size of thrombus formation.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, higenamine might increase the levels and clinical effects of drugs metabolized by CYP2D6.
In vitro research shows that higenamine inhibits CYP2D6 enzymes. However, this effect has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, higenamine might increase the levels and clinical effects drugs metabolized by CYP3A4.
In vitro research shows that higenamine inhibits CYP3A4 enzymes by 21%. However, this effect has not been reported in humans.
Stimulant Drugs
Theoretically, higenamine might increase the risk of cardiovascular toxicity when taken with stimulant drugs.
Higenamine has stimulant effects due to agonist activity at beta2-adrenoreceptors. In cardiac muscle, higenamine appears to have a positive inotropic effect and increase heart rate. However, it does not appear to increase blood pressure.
Propranolol (Inderal)
Theoretically, the positive inotropic effects of higenamine might be reduced by propranolol.
Animal research shows that higenamine has a positive inotropic effect on the heart, and administering propranolol appears to block this cardiac effect. In animals, propranolol also appears to inhibit corpus cavernosum relaxation induced by higenamine.
Vitamin E, Powder
Alkylating Agents
Theoretically, antioxidant effects of vitamin E might reduce the effectiveness of alkylating agents.
There's concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin E have on chemotherapy. Advise patients to consult their oncologist before using vitamin E supplements, especially in high doses.
Anticoagulant/Antiplatelet Drugs
Concomitant use of vitamin E and anticoagulant or antiplatelet agents might increase the risk of bleeding.
Vitamin E seems to inhibit of platelet aggregation and antagonize the effects of vitamin K-dependent clotting factors. These effects appear to be dose-dependent, and are probably only likely to be clinically significant with doses of at least 800 units daily. Mixed tocopherols, such as those found in food, might have a greater antiplatelet effect than alpha-tocopherol. RRR alpha-tocopherol (natural vitamin E) 1000 IU daily antagonizes vitamin K-dependent clotting factors. Advise patients to avoid high doses of vitamin E, especially in people with low vitamin K intake or other risk factors for bleeding.
Antitumor Antibiotics
Theoretically, antioxidant effects of vitamin E might reduce the effectiveness of antitumor antibiotics.
There's concern that antioxidants could reduce the activity of antitumor antibiotic drugs such as doxorubicin, which generate free radicals. However, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that might interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin E have on chemotherapy involving antitumor antibiotics. Advise patients to consult their oncologist before using vitamin E supplements, especially in high doses.
Cyclosporine (Neoral, Sandimmune)
A specific form of vitamin E might increase absorption and levels of cyclosporine.
There is some evidence that one specific formulation of vitamin E (D-alpha-tocopheryl-polyethylene glycol-1000 succinate, TPGS, tocophersolan, Liqui-E) might increase absorption of cyclosporine. This vitamin E formulation forms micelles which seems to increase absorption of cyclosporine by 40% to 72% in some patients. However, this interaction is unlikely to occur with the usual forms of vitamin E.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, vitamin E might induce metabolism of CYP3A4, possibly reducing the levels CYP3A4 substrates.
Vitamin E appears to bind with the nuclear receptor, pregnane X receptor (PXR), which results in increased expression of CYP3A4. Although the clinical significance of this is not known, use caution when considering concomitant use of vitamin E and other drugs affected by these enzymes.
Selumetinib (Koselugo)
Taking selumetinib with vitamin E can result in a total daily dose of vitamin E that exceeds safe limits and therefore might increase the risk of bleeding.
Selumetinib contains 48-54 IU vitamin E per capsule. The increased risk of bleeding with vitamin E appears to be dose-dependent. Be cautious when using selumetinib in combination with supplemental vitamin E, especially in patients at higher risk of bleed, such as those with chronic conditions and those taking antiplatelet drugs.
Warfarin (Coumadin)
Using vitamin E with warfarin might increase the risk of bleeding.
Due to interference with production of vitamin K-dependent clotting factors, use of more than 400 IU of vitamin E daily with warfarin might increase prothrombin time (PT), INR, and the risk of bleeding,. At a dose of 1000 IU per day, vitamin E can antagonize vitamin K-dependent clotting factors even in people not taking warfarin. Limited clinical evidence suggests that doses up to 1200 IU daily may be used safely by patients taking warfarin, but this may not be applicable in all patient populations.
Niacin
Vitamin E might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises high-density lipoprotein (HDL) cholesterol levels in people with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50%. Vitamin E alone combined with a statin does not seem to decrease HDL levels. It is not known whether the adverse effect on HDL is due to one of the other antioxidants or to the combination. It also is not known whether it will occur in other patient populations.
Niacin
Alcohol (Ethanol)
Concomitant use of alcohol and niacin might increase the risk of flushing and hepatotoxicity.
Alcohol can exacerbate the flushing and pruritus associated with niacin. Large doses of niacin might also exacerbate liver dysfunction associated with chronic alcohol use. A case report describes delirium and lactic acidosis in a patient taking niacin 3 grams daily who ingested 1 liter of wine. Advise patients to avoid large amounts of alcohol while taking niacin.
Allopurinol (Zyloprim)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as allopurinol.
Large doses of niacin can reduce urinary excretion of uric acid, potentially resulting in hyperuricemia. Doses of uricosurics such as allopurinol might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Anticoagulant/Antiplatelet Drugs
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Several cases of clotting factor synthesis deficiency and coagulopathy have been reported in patients taking sustained-release niacin. Also, thrombocytopenia has been reported in patients treated with niacin or niacin plus lovastatin.
Antidiabetes Drugs
Niacin can increase blood glucose levels and may diminish the effects of antidiabetes drugs.
Niacin impairs glucose tolerance in a dose-dependent manner, probably by causing or aggravating insulin resistance and increasing hepatic production of glucose. In diabetes patients, niacin 4.5 grams daily for 5 weeks can increase plasma glucose by an average of 16% and glycated hemoglobin (HbA1c) by 21%. However, lower doses of 1.5 grams daily or less appear to have minimal effects on blood glucose. In some patients, glucose levels increase when niacin is started, but then return to baseline when a stable dose is reached. Up to 35% of patients with diabetes may need adjustments in hypoglycemic therapy when niacin is added.
Antihypertensive Drugs
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
The vasodilating effects of niacin can cause hypotension. Furthermore, some clinical evidence suggests that a one-hour infusion of niacin can reduce systolic, diastolic, and mean blood pressure in hypertensive patients. This effect is not observed in normotensive patients.
Bile Acid Sequestrants
Bile acid sequestrants can bind niacin and decrease absorption. Separate administration by 4-6 hours to avoid an interaction.
In vitro studies show that colestipol (Colestid) binds about 98% of available niacin and cholestyramine (Questran) binds 10% to 30%.
Gemfibrozil (Lopid)
Theoretically, concomitant use of niacin and gemfibrozil might increase the risk of myopathy in some patients.
A case of myopathy from concomitant use of niacin and gemfibrozil has been reported. Niacin alone has also been associated with cases of myopathy. Using gemfibrozil with niacin might further increase the risk of developing myopathy.
Hepatotoxic Drugs
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Niacin has been associated with cases of liver toxicity, especially when used in pharmacologic doses. Sustained-release niacin preparations appear to be associated with a higher risk of hepatotoxicity than immediate-release niacin.
Hmg-Coa Reductase Inhibitors ("Statins")
Theoretically, concomitant use of niacin and statins might increase the risk of myopathy and rhabdomyolysis in some patients.
Some case reports have raised concerns that niacin might increase the risk of myopathy and rhabdomyolysis when combined with statins. However, a significantly increased risk of myopathy has not been demonstrated in clinical trials, including those using an FDA-approved combination of lovastatin and niacin (Advicor).
Probenecid (Benemid)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as probenecid.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as probenecid might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Sulfinpyrazone (Anturane)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as sulfinpyrazone.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as sulfinpyrazone might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Thyroid Hormone
Theoretically, niacin might antagonize the therapeutic effects of thyroid hormones.
Clinical research and case reports suggests that taking niacin can reduce serum levels of thyroxine-binding globulin by up to 25% and moderately reduce levels of thyroxine (T4). Patients taking thyroid hormone for hypothyroidism might need dose adjustments when using niacin.
Transdermal Nicotine (Nicoderm)
Theoretically, concomitant use of niacin and transdermal nicotine might increase the risk of flushing and dizziness.
Niacin and nicotine can both cause flushing and dizziness.
Warfarin (Coumadin)
There is limited evidence that niacin may increase the anticoagulant effects of warfarin.
In a case report, a patient on warfarin developed an elevated international normalized ratio (INR) of 3.9 after taking niacin for two weeks. The patient's INR was previously stable, ranging between 2 and 3 in recent months, and no other medication changes were identified. The elevated INR returned to therapeutic range within 4 days following the discontinuation of niacin.
Aspirin
Large doses of aspirin might alter the clearance of niacin.
Aspirin is often used with niacin to reduce niacin-induced flushing. Doses of 80-975 mg aspirin have been used, but 325 mg appears to be optimal. Aspirin also seems to reduce the clearance of niacin by competing for glycine conjugation. Taking aspirin 1 gram seems to reduce niacin clearance by 45%. This is probably a dose-related effect and not clinically significant with the more common aspirin dose of 325 mg.
Guarana
Ephedrine
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Guarana contains caffeine. Use of ephedrine with caffeine can increase the risk of stimulatory adverse effects. There is evidence that using ephedrine with caffeine might increase the risk of serious life-threatening or debilitating adverse effects such as hypertension, myocardial infarction, stroke, seizures, and death.
Adenosine (Adenocard)
Theoretically, guarana might decrease the vasodilatory effects of adenosine and interfere with its use prior to stress testing.
Guarana contains caffeine. Caffeine is a competitive inhibitor of adenosine at the cellular level. However, caffeine does not seem to affect supplemental adenosine because high interstitial levels of adenosine overcome the antagonistic effects of caffeine. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. However, methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Anticoagulant/Antiplatelet Drugs
Theoretically, guarana may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro and animal research suggests that guarana extract can inhibit platelet aggregation. This effect may be due to the caffeine in guarana, which is also reported to have antiplatelet activity. This interaction has not been reported in humans.
Beta-Adrenergic Agonists
Theoretically, concomitant use might increase the clinical effects of beta-adrenergic agonists.
Guarana contains caffeine. Theoretically, concomitant use of large amounts of caffeine might increase cardiac inotropic effects of beta-agonists.
Carbamazepine (Tegretol)
Theoretically, guarana might reduce the effects of carbamazepine and increase the risk for convulsions.
Animal research suggests that taking caffeine can lower the anticonvulsant effects of carbamazepine and can induce seizures when given to animals in doses above 400 mg/kg. Human research has shown that taking caffeine 300 mg in three divided doses along with carbamazepine 200 mg reduces the bioavailability of carbamazepine by 32% and prolongs the plasma half-life of carbamazepine two-fold in healthy individuals.
Cimetidine (Tagamet)
Theoretically, concomitant use might increase the effects and adverse effects of caffeine in guarana.
Guarana contains caffeine. Cimetidine decreases the rate of caffeine clearance by 31% to 42%.
Clozapine (Clozaril)
Theoretically, guarana might increase the levels and adverse effects of clozapine and acutely exacerbate psychotic symptoms.
Guarana contains caffeine. Caffeine can increase the effects and toxicity of clozapine. Caffeine doses of 400-1000 mg per day inhibit clozapine metabolism. Clozapine is metabolized by cytochrome P450 1A2 (CYP1A2). Researchers speculate that caffeine might inhibit CYP1A2. However, there is no reliable evidence that caffeine affects CYP1A2. There is also speculation that genetic factors might make some patients more sensitive to the interaction between clozapine and caffeine.
Dipyridamole (Persantine)
Theoretically, guarana might decrease the vasodilatory effects of dipyridamole and interfere with its use prior to stress testing.
Guarana contains caffeine. Caffeine might inhibit dipyridamole-induced vasodilation. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. Methylxanthines appear more likely to interfere with dipyridamole than adenosine-induced stress testing.
Disulfiram (Antabuse)
Theoretically, disulfiram might increase the risk of adverse effects from caffeine.
In human research, disulfiram decreases the clearance and increases the half-life of caffeine.
Diuretic Drugs
Theoretically, using guarana with diuretic drugs might increase the risk of hypokalemia.
Guarana contains caffeine. Caffeine, especially in excessive amounts, can reduce potassium levels due to stimulation of the sodium-potassium pump. Diuretics can also lower potassium levels.
Estrogens
Theoretically, estrogens might increase the levels and adverse effects of caffeine.
Guarana contains caffeine. Estrogen inhibits caffeine metabolism.
Ethosuximide (Zarontin)
Theoretically, guarana might reduce the effects of ethosuximide and increase the risk for convulsions.
Guarana contains caffeine. Animal research shows that caffeine 92.4 mg/kg can decrease the anticonvulsant activity of ethosuximide. This effect has not been observed in humans.
Felbamate (Felbatol)
Theoretically, guarana might reduce the effects of felbamate and increase the risk for convulsions.
Guarana contains caffeine. Animal research shows that a high dose of caffeine 161.7 mg/kg can decreases the anticonvulsant activity of felbamate. This effect has not been observed in humans.
Flutamide (Eulexin)
Theoretically, guarana might increase the levels and adverse effects of flutamide.
Guarana contains caffeine. In vitro evidence shows that caffeine can inhibit the metabolism of flutamide. However, this effect has not been reported in humans.
Fluvoxamine (Luvox)
Theoretically, fluvoxamine might increase the levels and adverse effects of caffeine.
Guarana contains caffeine. Fluvoxamine reduces caffeine metabolism.
Lithium
Theoretically, abrupt guarana withdrawal might increase the levels and adverse effects of lithium.
Guarana contains caffeine. Theoretically, abrupt caffeine withdrawal might increase serum lithium levels. There are two case reports of lithium tremor that worsened upon abrupt coffee withdrawal.
Monoamine Oxidase Inhibitors (Maois)
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Guarana contains caffeine. Caffeine has been shown to inhibit MAO-A and -B in laboratory studies. Concomitant intake of large amounts of caffeine with MAOIs might precipitate a hypertensive crisis. In a case report, a patient that consumed 10-12 cups of caffeinated coffee and took the MAOI tranylcypromine presented with severe hypertension. Hypertension was resolved after the patient switched to drinking decaffeinated coffee.
Nicotine
Theoretically, concomitant use might increase the risk of hypertension.
Guarana contains caffeine. Concomitant use of caffeine and nicotine has been shown to have additive cardiovascular effects, including increased heart rate and blood pressure. Blood pressure was increased by 10.8/12.4 mmHg when the agents were used concomitantly.
Pentobarbital (Nembutal)
Theoretically, guarana might decrease the effects of pentobarbital.
Guarana contains caffeine. In vivo evidence suggests that caffeine can negate the hypnotic effects of pentobarbital in humans. However, animal research suggests that guarana does not alter the hypnotic effect of pentobarbital.
Phenobarbital (Luminal)
Theoretically, guarana might reduce the effects of phenobarbital and increase the risk for convulsions.
Guarana contains caffeine. Animal research shows that caffeine can decrease the anticonvulsant activity of phenobarbital. The exact mechanism of this interaction is unclear.
Phenylpropanolamine
Theoretically, phenylpropanolamine might increase the risk of hypertension, as well as the levels and adverse effects of caffeine.
Guarana contains caffeine. Concomitant use of phenylpropanolamine and caffeine might cause an additive increase in blood pressure. Phenylpropanolamine also seems to increase caffeine serum levels.
Phenytoin (Dilantin)
Theoretically, guarana might reduce the effects of phenytoin and increase the risk for convulsions.
Guarana contains caffeine. Animal research shows that caffeine can decrease the anticonvulsant activity of phenytoin. The effect does not seem to be related to the seizure threshold-lowering effects of caffeine. However, the exact mechanism of this interaction is unclear.
Pioglitazone (Actos)
Theoretically, guarana might increase the levels and clinical effects of pioglitazone.
Guarana contains caffeine. Animal research suggests that caffeine can modestly increase the maximum concentration, area under the curve, and half-life of pioglitazone, and also reduce its clearance. This increased the antidiabetic effects of pioglitazone. However, the exact mechanism of this interaction is unclear.
Riluzole (Rilutek)
Theoretically, concomitant use might increase the levels and adverse effects of both caffeine and riluzole.
Guarana contains caffeine. Caffeine and riluzole are both metabolized by cytochrome P450 1A2 (CYP1A2), and concomitant use might reduce the metabolism of one or both agents.
Stimulant Drugs
Theoretically, concomitant use might increase stimulant adverse effects.
Guarana contains caffeine. Due to the central nervous system (CNS) stimulant effects of caffeine, concomitant use with stimulant drugs can increase the risk of adverse effects.
Octopamine Hydrochloride
Antihypertensive Drugs
In humans, octopamine 450-600 mg daily increases blood pressure in hypotensive patients. However, evidence from animal research suggests that octopamine can lower blood pressure. Theoretically, concomitant use of octopamine and antihypertensive drugs might potentiate and/or reduce the activity of antihypertensive drugs.
Some antihypertensive drugs include captopril (Capoten), enalapril (Vasotec), losartan (Cozaar), valsartan (Diovan), diltiazem (Cardizem), Amlodipine (Norvasc), hydrochlorothiazide (HydroDiuril), furosemide (Lasix), and many others.
Monoamine Oxidase Inhibitors (Maois)
Octopamine is metabolized by monoamine oxidase. Theoretically, concurrent use of MAOIs with octopamine might increase the effects and side effects of octopamine. Tell patients taking MAOIs to avoid using octopamine. Some MAOIs include phenelzine (Nardil), tranylcypromine (Parnate), and others.
Stimulant Drugs
Octopamine is thought to have stimulant effects. Theoretically, taking octopamine with other stimulant drugs might increase the risk of hypertension and adverse cardiovascular effects.
Some stimulant drugs include amphetamine, caffeine, diethylpropion (Tenuate), methylphenidate, phentermine (Ionamin), pseudoephedrine (Sudafed, others), and many others.
N Methyl Tyramine HCl
Antihypertensive Drugs
In animal research, N-methyltyramine increased blood pressure. This has not been shown in humans. Theoretically, concomitant use of N-methyltyramine and antihypertensive drugs might reduce the effects of antihypertensive drugs.
Some antihypertensive drugs include captopril (Capoten), enalapril (Vasotec), losartan (Cozaar), valsartan (Diovan), diltiazem (Cardizem), Amlodipine (Norvasc), hydrochlorothiazide (HydroDiuril), furosemide (Lasix), and many others.
Stimulant Drugs
N-methyltyramine is thought to have stimulant effects. However, this has not been shown in humans and laboratory research does not support the proposed stimulant effects of N-methyltyramine. Theoretically, taking N-methyltyramine with other stimulant drugs might increase the risk of hypertension and adverse cardiovascular effects. Until more is known, avoid taking N-methyltyramine with stimulant drugs.
Some stimulant drugs include amphetamine, caffeine, diethylpropion (Tenuate), methylphenidate, phentermine (Ionamin), pseudoephedrine (Sudafed, others), and many others.
N-Isopropylnorsynephrine HCl
Antihypertensive Drugs
Theoretically, isopropylnorsynephrine might decrease the effects of antihypertensive drugs.
In vitro research shows that isopropylnorsynephrine is a highly selective, direct-acting beta-adrenergic receptor agonist with positive chronotropic effects, and hypertension has been reported in patients taking combination products containing isopropylnorsynephrine and other stimulants.
Stimulant Drugs
Theoretically, taking isopropylnorsynephrine with stimulant drugs might have additive effects and increase the risk of adverse cardiovascular effects.
Isopropylnorsynephrine is an investigational beta-agonist and a derivative of synephrine and octopamine, which are stimulant constituents of bitter orange. In vitro research shows that isopropylnorsynephrine is a highly selective, direct-acting beta-adrenergic receptor agonist with positive chronotropic effects. Theoretically, isopropylnorsynephrine may also have stimulant effects.
Methyl Hordenine HCl
Monoamine Oxidase Inhibitors (Maois)
Hordenine is structurally similar to tyramine In vitro research shows that hordenine is a selective substrate for monoamine oxidase-B in the liver. Theoretically, concomitant use of hordenine with MAOIs might increase blood pressure, potentially leading to a hypertensive crisis.
Some MAOIs include isocarboxazid (Marplan), phenelzine (Nardil), selegiline (Eldepryl, Emsam, Zelapar), and tranylcypromine (Parnate).
Stimulant Drugs
Hordenine is structurally similar to N-methyltyramine and synephrine, constituents in bitter orange known to have stimulant properties. Theoretically, taking hordenine with drugs with stimulant properties might increase the risk of hypertension and other adverse cardiovascular effects.
Some of these drugs include amphetamine, caffeine, methylphenidate, pseudoephedrine, and many others.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Hordenine weakly inhibits cytochrome P450 2D6 (CYP2D6) enzymes in vitro. Theoretically, hordenine might increase the levels of CYP2D6 substrates.
Some of drugs that are CYP2D6 substrates include amitriptyline (Elavil), clozapine (Clozaril), codeine, desipramine (Norpramin), donepezil (Aricept), fentanyl (Duragesic), flecainide (Tambocor), fluoxetine (Prozac), meperidine (Demerol), methadone (Dolophine), metoprolol (Lopressor, Toprol XL), olanzapine (Zyprexa), ondansetron (Zofran), tramadol (Ultram), trazodone (Desyrel), and others.
Adaptogen Max
Anticoagulant/Antiplatelet Drugs
Theoretically, jiaogulan might increase the risk of bleeding when taken with anticoagulant or antiplatelet drugs.
In vitro research suggests that jiaogulan has antiplatelet effects.
Antidiabetes Drugs
Theoretically, jiaogulan might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Clinical research shows that jiaogulan can lower blood glucose levels.
Immunosuppressants
Theoretically, jiaogulan might decrease the effectiveness of immunosuppressive therapy.
Clinical and animal studies suggest that jiaogulan can stimulate the immune system.
Theacrine
Cns Depressants
Theoretically, theacrine might alter the effects of CNS depressants.
Animal research shows that low doses of theacrine have sedating effects, whereas high doses might have stimulant effects. Depending on the dose of theacrine used, it might increase or decrease the effects of CNS depressants. However, these effects have not yet been reported in humans.
Capsicum annuum
Anticoagulant/Antiplatelet Drugs
Theoretically, capsicum may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro research shows that capsicum might increase the effects of antiplatelet drugs. Also, population research shows that capsicum is associated with an increased risk of self-reported bleeding in patients taking warfarin. However, clinical research shows that taking a single dose of capsaicin (Asian Herbex Ltd.), the active ingredient in capsicum, 400-800 mcg orally in combination with aspirin 500 mg does not decrease platelet aggregation when compared with taking aspirin 500 mg alone. Also, there was no notable effect on measures of platelet aggregation with capsaicin. It is unclear whether capsaicin must be used in more than a single dose to affect platelet aggregation.
Antidiabetes Drugs
Theoretically, taking capsicum with antidiabetes drugs might increase the risk of hypoglycemia.
Preliminary clinical research shows that consuming capsicum 5 grams along with a glucose drink attenuates the rise in plasma glucose after 30 minutes by 21%, decreases the 2-hour postprandial area under the curve of plasma glucose by 11%, and increases the 2-hour postprandial area under the curve of plasma insulin by 58% in healthy individuals when compared with placebo. Other clinical research shows that taking capsicum 5 mg daily for 28 days significantly reduces postprandial blood glucose and insulin levels, but not fasting blood glucose and insulin levels, in patients with gestational diabetes.
Aspirin
Theoretically, taking capsicum with aspirin might reduce the bioavailability of aspirin.
Animal research shows that acute or chronic intake of capsicum pepper reduces oral aspirin bioavailability. This has not been shown in humans.
Theophylline
Theoretically, taking capsicum with theophylline might increase the levels and adverse effects of theophylline.
In animal research, oral administration of capsicum reduced excretion of theophylline. However, capsicum does not seem to affect the pharmacokinetics of theophylline when administered intravenously.
Ace Inhibitors (Aceis)
Theoretically, using topical capsaicin may increase the risk of ACE inhibitor-induced cough.
There is one case report of a topically applied capsaicin cream contributing to the cough reflex in a patient using an ACEI. However, it is unclear if this interaction is clinically significant.
Ciprofloxacin (Cipro)
Theoretically, taking capsicum with ciprofloxacin might increase levels and adverse effects of ciprofloxacin.
Animal research shows that concomitant use of capsaicin, the active constituent of capsicum, and ciprofloxacin increases the bioavailability of ciprofloxacin by up to 70%.
Methyl-Synephrine HCl
Beta-Adrenergic Agonists
Methylsynephrine has beta agonist activity. Theoretically, concomitant use of large amounts of methylsynephrine might increase the cardiac inotropic effects of beta-agonists. Beta-adrenergic agonists include albuterol (Ventolin, Proventil), metaproterenol (Alupent), terbutaline (Brethine, Bricanyl), and isoproterenol (Isuprel).
Stimulant Drugs
Methylsynephrine has cardiac stimulant effects. Theoretically, taking methylsynephrine with other stimulant drugs might increase the risk of hypertension and adverse cardiovascular effects.
Some stimulant drugs include amphetamine, caffeine, diethylpropion (Tenuate), methylphenidate, phentermine (Ionamin), pseudoephedrine (Sudafed, others), and many others.
Vitamin B12
Metformin (Glucophage)
Metformin, a common medication used to manage type 2 diabetes, has been associated with lower vitamin B12 levels in some individuals. Prolonged use of metformin can interfere with the absorption of B12 in the digestive system, potentially leading to a deficiency in this essential vitamin.
Brand information
Manufacturer and brand details for Jacked & Sexy, from the product label.
Jacked & Sexy by Core Labs X: Common Questions
Does Jacked & Sexy by Core Labs X interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take this while pregnant or breastfeeding?
Does this product actually work for muscle building or fat loss?
What are the common side effects?
Why is this product banned in some sports?
What makes this so risky with medications?
Is it safe to take with my antidepressant?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Jacked & Sexy is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Jacked & Sexy’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin B12
Interacts with 20 drugsVitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very helpful for people who are deficient — su...
Read the full Vitamin B12 monograph → Herb & supplement monographHigenamine
Interacts with 891 drugsHigenamine is a plant-based stimulant compound added to many weight-loss and pre-workout supplements, but there is very little human evidence that it works and real concerns about heart and...
Read the full Higenamine monograph → Herb & supplement monographBitter Orange
Interacts with 957 drugsBitter orange is a citrus fruit whose extracts contain synephrine, a mild stimulant often added to weight-loss and energy supplements. Evidence that it works for weight loss or performance i...
Read the full Bitter Orange monograph → Herb & supplement monographYohimbe
Interacts with 1,125 drugsYohimbe is a West African tree bark that contains yohimbine, a compound mainly promoted for erectile dysfunction and as an aphrodisiac. A prescription form of yohimbine has some evidence for...
Read the full Yohimbe monograph → Herb & supplement monographN-methyltyramine
Interacts with 344 drugsN-methyltyramine is a natural compound related to tyramine that is found in bitter orange, barley, and other plants, and it is often added to weight-loss and pre-workout supplements. Solid h...
Read the full N-methyltyramine monograph → Herb & supplement monographMethylsynephrine
Interacts with 191 drugsMethylsynephrine (also called oxilofrine) is a synthetic stimulant sometimes added to weight-loss and pre-workout products, but it is not a legal or approved dietary ingredient in the United...
Read the full Methylsynephrine monograph → Herb & supplement monographIsopropylnorsynephrine
Interacts with 344 drugsIsopropylnorsynephrine is a synthetic stimulant chemically related to synephrine, marketed mainly in weight-loss and pre-workout supplements. It has very little human safety or effectiveness...
Read the full Isopropylnorsynephrine monograph → Herb & supplement monographHordenine
Interacts with 329 drugsHordenine is a natural alkaloid found in barley and some cacti that is marketed as a stimulant for energy, focus, and fat loss, but solid human evidence for these benefits is lacking. Its sa...
Read the full Hordenine monograph → Herb & supplement monographCapsicum
Interacts with 239 drugsCapsicum (chili pepper) contains capsaicin, which is best known and best studied as a topical treatment for certain types of pain. Topical capsaicin products are supported by reasonable evid...
Read the full Capsicum monograph → Herb & supplement monographGuarana
Interacts with 655 drugsGuarana is an Amazonian seed that is naturally high in caffeine, which explains most of its stimulant and energy effects. While it may give a short-term boost in alertness and reduce fatigue...
Read the full Guarana monograph → Herb & supplement monographGreen Tea
Interacts with 1,293 drugsGreen tea is a popular beverage rich in antioxidants called catechins, and drinking it in normal amounts is considered safe for most people. Concentrated green tea extracts are a different s...
Read the full Green Tea monograph → Herb & supplement monographTheacrine
Interacts with 248 drugsTheacrine is a caffeine-like compound found naturally in certain tea plants and is sold in supplements for energy, focus, and mood. Early human studies suggest it may give a stimulant-like b...
Read the full Theacrine monograph → Herb & supplement monographOctopamine
Interacts with 352 drugsOctopamine is a stimulant-like compound found in small amounts in some plants (such as bitter orange) and made naturally in the body. It is marketed mostly in weight-loss and sports suppleme...
Read the full Octopamine monograph → Herb & supplement monographDiiodothyronine
Diiodothyronine (T2) is a thyroid hormone metabolite sold as a fat-loss and metabolism supplement, mostly in the bodybuilding world. Human evidence for its safety and effectiveness is very l...
Read the full Diiodothyronine monograph → Herb & supplement monographJiaogulan
Interacts with 327 drugsJiaogulan is a climbing vine used in traditional Chinese medicine as an adaptogen and for heart, blood sugar, and cholesterol support. Early human and animal studies are promising for some u...
Read the full Jiaogulan monograph → Herb & supplement monographSulbutiamine
Sulbutiamine is a man-made, fat-soluble form of vitamin B1 (thiamine) developed in Japan, often taken for fatigue and to support mental energy and focus. Human evidence is limited and mostly...
Read the full Sulbutiamine monograph → Herb & supplement monographVitamin B6
Interacts with 210 drugsVitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is best known for helping with pregnancy-rel...
Read the full Vitamin B6 monograph → Herb & supplement monographAlpha-gpc
Interacts with 16 drugsAlpha-GPC is a choline-containing compound used mainly for memory, brain health, and as a choline source. There is some evidence it may help cognition in people with dementia, but evidence i...
Read the full Alpha-gpc monograph → Herb & supplement monographCowhage
Interacts with 193 drugsCowhage (Mucuna pruriens) is a tropical legume best known as a natural source of L-dopa, the compound the body turns into dopamine. It is most studied for Parkinson's disease symptoms and ma...
Read the full Cowhage monograph → Herb & supplement monographPhenethylamine (pea)
Interacts with 187 drugsPhenethylamine (PEA) is a natural compound made in the body and found in foods like chocolate; supplements are marketed for mood, focus, and energy. Reliable human research on the supplement...
Read the full Phenethylamine (pea) monograph → Herb & supplement monographDeanol
Interacts with 219 drugsDeanol (DMAE) is a compound related to choline that is marketed for memory, focus, and mood, but solid human evidence for most of these uses is limited or mixed. It can cause side effects in...
Read the full Deanol monograph → Herb & supplement monographRhodiola
Interacts with 1,271 drugsRhodiola is an herb traditionally used to fight fatigue and help the body cope with stress. Some small studies suggest it may modestly reduce fatigue and improve mood, but the evidence is li...
Read the full Rhodiola monograph → Herb & supplement monographGrape
Interacts with 910 drugsGrapes and grape products like grape seed extract contain antioxidant compounds such as resveratrol and proanthocyanidins that may support heart and blood vessel health. While the food is he...
Read the full Grape monograph → Herb & supplement monographNiacin
Interacts with 727 drugsNiacin (vitamin B3) is an essential nutrient your body needs for energy and metabolism, and deficiency is uncommon in most developed countries. Prescription-strength niacin has been used to...
Read the full Niacin monograph → Herb & supplement monographBlack Pepper
Interacts with 1,019 drugsBlack pepper is a common kitchen spice that is generally safe in the amounts used in food. Its extract, piperine, is mostly added to supplements to help the body absorb other ingredients (li...
Read the full Black Pepper monograph → Herb & supplement monographVitamin E
Interacts with 764 drugsVitamin E is an essential fat-soluble vitamin and antioxidant that most people get in adequate amounts from a normal diet. Supplements can help correct a true deficiency, but high-dose vitam...
Read the full Vitamin E monograph →Sources & How We Checked
Jacked & Sexy's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 890 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Vitamin B12 30 references
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Hartman TJ, Woodson K, Stolzenberg-Solomon R, et al. Association of the B-vitamins pyridoxal 5'-phosphate (B6), B12, and folate with lung cancer risk in older men. Am J Epidemiol 2001;153:688-94.. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Lange H, Suryapranata H, De Luca G, et al. Folate therapy and in-stent restenosis after coronary stenting. N Engl J Med 2004;350:2673-81. PubMed
- Collin, S. M., Metcalfe, C., Refsum, H., Lewis, S. J., Zuccolo, L., Smith, G. D., Chen, L., Harris, R., Davis, M., Marsden, G., Johnston, C., Lane, J. A., Ebbing, M., Bonaa, K. H., Nygard, O., Ueland, P. M., Grau, M. V., Baron, J. A., Donovan, J. L., Nea
- Geissbuhler, P., Mermillod, B., and Rapin, C. H. Elevated serum vitamin B12 levels associated with CRP as a predictive factor of mortality in palliative care cancer patients: a prospective study over five years. J.Pain Symptom.Manage. 2000;20(2):93-103. PubMed
- Salles, N., Herrmann, F., Sakbani, K., Rapin, C. H., and Sieber, C. High vitamin B12 level: a strong predictor of mortality in elderly inpatients. J Am Geriatr.Soc 2005;53(5):917-918.
- Looker, H. C., Fagot-Campagna, A., Gunter, E. W., Pfeiffer, C. M., Sievers, M. L., Bennett, P. H., Nelson, R. G., Hanson, R. L., and Knowler, W. C. Homocysteine and vitamin B(12) concentrations and mortality rates in type 2 diabetes. Diabetes Metab Res R
- Uhl, W., Nolting, A., Golor, G., Rost, K. L., and Kovar, A. Safety of hydroxocobalamin in healthy volunteers in a randomized, placebo-controlled study. Clin Toxicol (Phila) 2006;44 Suppl 1:17-28. PubMed
- Borron, S. W., Baud, F. J., Barriot, P., Imbert, M., and Bismuth, C. Prospective study of hydroxocobalamin for acute cyanide poisoning in smoke inhalation. Ann Emerg.Med 2007;49(6):794-801, 801. PubMed
- Borron, S. W., Baud, F. J., Megarbane, B., and Bismuth, C. Hydroxocobalamin for severe acute cyanide poisoning by ingestion or inhalation. Am J Emerg.Med 2007;25(5):551-558. PubMed
- Lewis, J. G. Gout, Steatorrhoea, and Megaloblastic Anaemia. Ann Rheum.Dis 1962;21(3):284-286. PubMed
- Tal, S., Shavit, Y., Stern, F., and Malnick, S. Association between vitamin B12 levels and mortality in hospitalized older adults. J Am Geriatr.Soc 2010;58(3):523-526. PubMed
- Baztan, J. J., Gavidia, J. J., Gomez-Pavon, J., Esteve, A., and Ruiperez, I. High vitamin B12 levels and in-hospital mortality. J Am Geriatr.Soc 2010;58(11):2237-2238. PubMed
- Omboni, E., Checchini, M., and Longoni, F. [Hypopotassemia and megaloblastic anemia. Presentation of a case]. Minerva Med 8-31-1987;78(16):1255-1257.
- Aalfs As, Scholvinck LH, Horvath B. Acneiform eruption in a 5-year old due to vitamin B12 supplementation. Eur J Dermatol 2013;23(5):726-7. PubMed
- Balta I, Ozuguz P. Vitamin B12-induced acneiform eruption. Cutan Ocul Toxicol 2014;33(2):94-5. PubMed
- Carman KB, Belgemen T, Yis U. Involuntary movements misdiagnosed as seizure during vitamin B12 treatment. Pediatr Emerg Care 2013;29(11):1223-4. PubMed
- Djuric V, Bogic M, Popadic AP, et al. Anaphylactic reaction to hydroxycobalamin with tolerance to cyanocobalamin. Ann Allergy Asthma Immunol 2012;108(3):207-8. PubMed
- Kartel O, Gulec M, Demirel F, et al. Vitamin B12 allergy and successful desensitization with cyanocobalamin: A case report. Allergol Immunopath (Madr) 2012;40(5):324-5.
- Patiroglu T, Unal E, Yildirim S. Infantile tremor syndrome associated with cobalamin therapy: A case report. Clin Neurol Neurosurg 2013;115(9):1903-5. PubMed
- Schulte S, Barkema LW, Kardaun SH. Long-lasting atypical acneiform eruption with prominent comedones induced by hydroxocobalamin (vitamin B12). J Dtsch Dermatol Ges 2014;12(6):502-3.
- Zanus C, Alberini E, Costa P, et al. Involuntary movements after correction of vitamin B12 deficiency: A video-case report. Epileptic Disord 2012;14(2):174-80. PubMed
- Fanidi A, Carreras-Torres R, Larose TL, et al. Is high vitamin B12 status a cause of lung cancer? Int J Cancer. 2019 Sep 15;145(6):1499-1503. PubMed
- Fujita Y, Mizukami T, Maya Y, et al. Vitamin B12 allergy manifesting as lymphomatoid contact dermatitis. Eur J Dermatol. 2020;30(3):304-305. PubMed
- Dépret F, Hoffmann C, Daoud L, et al. Association between hydroxocobalamin administration and acute kidney injury after smoke inhalation: a multicenter retrospective study. Crit Care. 2019;23(1):421. PubMed
- Khairan P, Sobue T, Eshak ES, et al. Association of dietary intakes of vitamin B12, vitamin B6, folate, and methionine with the risk of esophageal cancer: the Japan Public Health Center-based (JPHC) prospective study. BMC Cancer 2021;21(1):982. PubMed
- Evans J, Pandya A, Ding Y, Qunibi WY. Hydroxocobalamin-Induced Oxalate Nephropathy in a Patient With Smoke Inhalation. Kidney Int Rep 2021;6(8):2228-2231. PubMed
- Lacombe V, Chabrun F, Lacout C, et al. Persistent elevation of plasma vitamin B12 is strongly associated with solid cancer. Sci Rep 2021;11(1):13361. PubMed
- Pegalajar-García MD, Cebolla-Verdugo M, Prados-Carmona Á, Llamas-Segura C, Navarro-Triviño FJ. Systemic allergic dermatitis to cobalt present in cyanocobalamin supplementation. Contact Dermatitis 2023;89(3):203-205. PubMed
Sulbutiamine 4 references
- Shah S. Adjuvant role of vitamin B analogue (sulbutiamine) with anti-infective treatment in infection associated asthenia. J Assoc Physicians India. 2003;51:891-5.
- Loo H, Poirier M, Ollat H, et al. [Effects of subutiamine (Arcalion 200) on psycho-behavioral inhibition in major depressive episodes]. Encephale. 2000;26(2):70-5.
- Kiew K, Wan Mohamad W, Ridzuan A, et al. Effects of sulbutiamine on diabetic polyneuropathy: an open randomized controlled study in type 2 diabetics. Malays J Med Sci. 2002;9(1):21-7.
- Sevim S, Kaleagasi H, Tasdelen B. Sulbutiamine shows promising results in reducing fatigue in patients with multiple sclerosis. Mult Scler Relat Disord. 2017;16:40-43. PubMed
Vitamin B6 32 references
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Geerling BJ, Dagnelie PC, Badart-Smook A, et al. Diet as a risk factor for the development of ulcerative colitis. Am J Gastroenterol 2000;95:1008-13. PubMed
- South M. Neonatal seizures after pyridoxine use -- reply. Lancet 1999;354:2083. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Baxter P, Aicardi J. Neonatal seizures after pyridoxine use. Lancet 1999;354:2082-3. PubMed
- Bendich A, Cohen M. Vitamin B6 safety issues. Ann N Y Acad Sci 1990;585:321-30.
- Schaumburg H, Kaplan J, Windebank A. Sensory neuropathy from pyridoxine abuse. A new megavitamin syndrome. N Engl J Med 1983;309:445-8. PubMed
- Gordon N. Pyridoxine dependency: an update. Dev Med Child Neurol 1997;39:63-5. PubMed
- Lewis PJ. Pain in the hand and wrist. Pyridoxine supplements may help patients with carpal tunnel syndrome. BMJ 1995;310:1534. PubMed
- Kaufman G. Pyridoxine against amiodarone-induced photosensitivity (letter). Lancet 1984;1:51-2. PubMed
- Mulrow JP, Mulrow CD, McKenna WJ. Pyridoxine and amiodarone-induced photosensitivity. Ann Intern Med 1985;103:68-9. PubMed
- Kawada A, Kashima A, Shiraishi H, et al. Pyridoxine-induced photosensitivity and hypophosphatasia. Dermatology 2000;201:356-60.. PubMed
- Vasile A, Goldberg R, Kornberg B. Pyridoxine toxicity: report of a case. J Am Osteopath Assoc 1984;83:790-1. DOI
- Hansson O, Sillanpaa M. Pyridoxine and serum concentration of phenytoin and phenobarbitone. Lancet 1976;1:256. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Chittumma P, Kaewkiattikun K, Wiriyasiriwach B. Comparison of the effectiveness of ginger and vitamin B6 for treatment of nausea and vomiting in early pregnancy: a randomized double-blind controlled trial. J Med Assoc Thai 2007;90:15-20.
- Hatzitolios, A., Iliadis, F., Katsiki, N., and Baltatzi, M. Is the anti-hypertensive effect of dietary supplements via aldehydes reduction evidence based? A systematic review. Clin Exp.Hypertens. 2008;30(7):628-639. PubMed
- Vasdev, S., Ford, C. A., Parai, S., Longerich, L., and Gadag, V. Dietary vitamin B6 supplementation attenuates hypertension in spontaneously hypertensive rats. Mol.Cell Biochem. 1999;200(1-2):155-162.
- de, Vogel S., Dindore, V., van, Engeland M., Goldbohm, R. A., van den Brandt, P. A., and Weijenberg, M. P. Dietary folate, methionine, riboflavin, and vitamin B-6 and risk of sporadic colorectal cancer. J Nutr 2008;138(12):2372-2378. PubMed
- Hagen, I., Nesheim, B. I., and Tuntland, T. No effect of vitamin B-6 against premenstrual tension. A controlled clinical study. Acta Obstet.Gynecol.Scand. 1985;64(8):667-670. PubMed
- Aybak, M., Sermet, A., Ayyildiz, M. O., and Karakilcik, A. Z. Effect of oral pyridoxine hydrochloride supplementation on arterial blood pressure in patients with essential hypertension. Arzneimittelforschung. 1995;45(12):1271-1273.
- Lal, K. J., Dakshinamurti, K., and Thliveris, J. The effect of vitamin B6 on the systolic blood pressure of rats in various animal models of hypertension. J Hypertens. 1996;14(3):355-363. PubMed
- Lauritzen CH, Reuter HD, Repges R, Bohnert K, and Schmidt U. Treatment of premenstrual tension syndrome with Vitex agnus castus. Controlled, double-blind study versus pyridoxine. Phytomed 1997;4(3):183-189. PubMed
- Fonseca VA, Lavery LA, Thethi TK, et al. Metanx in type 2 diabetes with peripheral neuropathy: A randomized trial. Am J Med 2013;126(2):141-9. PubMed
- Hankey GJ, Eikelboom JW, Yi Q, et al. Treatment with B vitamins and incidence of cancer in patients with previous stroke or transient ischemic attack: Results of a randomized placebo-controlled trial. Stroke 2012;43(6):1572-7. PubMed
- Hoyer-Kuhn H, Kohbrok S, Volland R, Franklin J, Hero B, Beck BB, Hoppe B. Vitamin B6 in primary hyperoxaluria I: first prospective trial after 40 years of practice. Clin J Am Soc Nephrol. 2014 Mar;9(3):468-77. PubMed
- Mahmoud A, Tabassum S, Al Enazi S, et al. Amelioration of levetiracetam-induced behavioral side effects by pyridoxine. A randomized double blind controlled study. Pediatr Neurol 2021;119:15-21. PubMed
- Gupta M, Gallante B, Bamberger JN, et al. Prospective randomized evaluation of idiopathic hyperoxaluria treatments. J Endourol 2021;35(12):1844-1851. PubMed
- Li H, Chen M, Liang S, et al. Excessive vitamin B6 during treatment is related to poor prognosis of patients with nasopharyngeal carcinoma: A U-shaped distribution suggests low dose supplement. Clin Nutr 2021;40(4):2293-2300. PubMed
- Tanigawa J, Nabatame S, Tominaga K, et al. High-dose pyridoxine treatment for inherited glycosylphosphatidylinositol deficiency. Brain Dev 2021;43(6):680-687. PubMed
- Committee on Practice Bulletins-Obstetrics. ACOG Practice Bulletin No. 189: Nausea And Vomiting Of Pregnancy. Obstet Gynecol. 2018;131(1):e15-e30. PubMed
Higenamine 14 references
- Tai YT, But PP, Young K, et al. Cardiotoxicity after accidental herb-induced aconite poisoning. Lancet 1992;340:1254-6. PubMed
- But PP, Tai YT, Young K. Three fatal cases of herbal aconite poisoning. Vet Hum Toxicol 1994;36:212-5.
- Lin CC, Chan TY, Deng JF. Clinical features and management of herb-induced aconitine poisoning. Ann Emerg Med 2004;43:574-9. PubMed
- Wagner H, Reiter M, Ferstl W. New drugs with cardiotonic activity. Part 1. Chemistry and pharmacology of the cardiotonic active principle of Annona squamosa L. Planta Med 1980;40:77-85.
- Park CW, Chang KC, Lim JK. Effects of higenamine on isolated heart adrenoceptor of rabbit. Arch Int Pharmacodyn Ther 1984;267:279-88.
- Liu WH, Zhou YP, Zeng GY. Effects of dl-demethylcoclaurine on experimental heart failure. Acta Pharm Sinica 1988;23:81-5.
- Yun-Choi HS, Pyo MK, Park KM, et al. Anti-thrombotic effects of higenamine. Planta Med 2001;67:619-22. PubMed
- Zhang Z, Liu X, Tao Z, et al. Effects of higeramine on hemodynamics and its tolerability and safety, an experimental study. Zhonghua Yi Xue Za Zhi 2002;82:352-5.
- Kam SC, Do JM, Choi JH, et al. The relaxation effect and mechanism of action of higenamine in the rat corpus cavernosum. Int J Impot Res 2012;24:77-83. PubMed
- Liu Y, Santillo MF. Cytochrome P450 2D6 and 3A4 enzyme inhibition by amine stimulants in dietary supplements. Drug Test Anal. 2016;8(3-4):307-10. PubMed
- Jeter J, DeZee KJ, Kennedy L. A Case of Paraspinal Muscle Rhabdomyolysis in a 22-Year-Old Male After Ingesting a Supplement Containing Higenamine. Mil Med. 2015;180(7):e847-9. PubMed
- Zhang N, Lian Z, Peng X, Li Z, Zhu H. Applications of Higenamine in pharmacology and medicine. J Ethnopharmacol. 2017;196:242-252. PubMed
- Cohen PA, Travis JC, Keizers PHJ, Boyer FE, Venhuis BJ. The stimulant higenamine in weight loss and sports supplements. Clin Toxicol (Phila). 2018:1-6. PubMed
- Rasic JS, Ivanovic ND, Andjelkovic MS, et al. Influence of higenamine on exercise performance of recreational female athletes: a randomized double-blinded placebo-controlled trial. Front Psychol 2021;12:633110. PubMed
Bitter Orange 47 references
- Penzak SR, Jann MW, Cold JA, et al. Seville (sour) orange juice: synephrine content and cardiovascular effects in normotensive adults. J Clin Pharmacol 2001;41:1059-63. PubMed
- Electronic Code of Federal Regulations. Title 21. Part 182 -- Substances Generally Recognized As Safe. Available at: https://www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfcfr/CFRSearch.cfm?CFRPart=182
- Calapai G, Firenzuoli F, Saitta A, et al. Antiobesity and cardiovascular toxic effects of Citrus aurantium extracts in the rat: A preliminary report. Fitoterapia 1999;70:586-92. DOI
- Keogh AM, Baron DW. Sympathomimetic abuse and coronary artery spasm. Br Med J 1985;291:940.
- Malhotra S, Bailey DG, Paine MF, Watkins PB. Seville orange juice-felodipine interaction: comparison with dilute grapefruit juice and involvement of furocoumarins. Clin Pharmacol Ther 2001;69:14-23. PubMed
- Pellati F, Benvenuti S, Melegari M, Firenzuoli F. Determination of adrenergic agonists from extracts and herbal products of Citrus aurantium L. var. amara by LC. J Pharm Biomed Anal 2002;29:1113-9. . PubMed
- Colker CM, Kalman DS, Torina GC, et al. Effects of Citrus aurantium extract, caffeine, and St. John's wort on body fat loss, lipid levels, and mood states in overweight healthy adults. Curr Ther Res 1999;60:145-153. DOI
- Penzak SR, Acosta EP, Turner M, et al. Effect of Seville orange juice and grapefruit juice on indinavir pharmacokinetics. J Clin Pharmacol 2002;42:1165-70. PubMed
- Edwards DJ, Fitzsimmons ME, Schuetz EG, et al. 6',7'-Dihydroxybergamottin in grapefruit juice and Seville orange juice: effects on cyclosporine disposition, enterocyte CYP3A4, and P-glycoprotein. Clin Pharmacol Ther 1999;65:237-44. PubMed
- Di Marco MP, Edwards DJ, Wainer IW, Ducharme MP. The effect of grapefruit juice and seville orange juice on the pharmacokinetics of dextromethorphan: the role of gut CYP3A and P-glycoprotein. Life Sci 2002;71:1149-60. PubMed
- Visentin V, Morin N, Fontana E, et al. Dual action of octopamine on glucose transport into adipocytes: inhibition via beta3-adrenoceptor activation and stimulation via oxidation by amine oxidases. J Pharmacol Exp Ther 2001;299:96-104.
- Nykamp DL, Fackih MN, Compton AL. Possible association of acute lateral-wall myocardial infarction and bitter orange supplement. Ann Pharmacother 2004;38:812-6. PubMed
- Fugh-Berman A, Myers A. Citrus aurantium, an ingredient of dietary supplements marketed for weight loss: Current status of clinical and basic Research. Exp Biol Med 2004;229:698-704.
- Suzuki O, Matsumoto T, Oya M, Katsumata Y. Oxidation of synephrine by type A and type B monoamine oxidase. Experientia 1979;35:1283-4. PubMed
- Nasir JM, Durning SJ, Ferguson M, et al. Exercise-induced syncope associated with QT prolongation and ephedra-free Xenadrine. Mayo Clin Proc 2004;79:1059-62.. PubMed
- Firenzuoli F, Gori L, Galapai C. Adverse reaction to an adrenergic herbal extract (Citrus aurantium). Phytomedicine 2005;12:247-8. PubMed
- Bouchard NC, Howland MA, Greller HA, et al. Ischemic stroke associated with use of an ephedra-free dietary supplement containing synephrine. Mayo Clin Proc 2005;80:541-5. PubMed
- Haller CA, Benowitz NL, Jacob P 3rd. Hemodynamic effects of ephedra-free weight-loss supplements in humans. Am J Med 2005;118:998-1003.. PubMed
- Bui LT, Nguyen DT, Ambrose PJ. Blood pressure and heart rate effects following a single dose of bitter orange. Ann Pharmacother 2006;40:53-7. PubMed
- Min B, Cios D, Kluger J, White CM. Absence of QTc-interval-prolonging or hemodynamic effects of a single dose of bitter-orange extract in healthy subjects. Pharmacotherapy 2005;25:1719-24. PubMed
- Gange CA, Madias C, Felix-Getzik EM, et al. Variant angina associated with bitter orange in a dietary supplement. Mayo Clin Proc 2006;81:545-8. PubMed
- Jordan S, Murty M, Pilon K. Products containing bitter orange or synephrine: suspected cardiovascular adverse reactions. Canadian Adverse Reaction Newsletter 2004;14:3-4.
- Burke J, Seda G, Allen D, Knee TS. A case of severe exercise-induced rhabdomyolysis associated with a weight loss dietary supplement. Mil Med 2007;172:656-8. PubMed
- Gray, S. and Woolf, A. D. Citrus aurantium used for weight loss by an adolescent with anorexia nervosa. J Adolesc.Health 2005;37(5):414-415. PubMed
- Haller, C. A., Duan, M., Jacob, P., III, and Benowitz, N. Human pharmacology of a performance-enhancing dietary supplement under resting and exercise conditions. Br J Clin Pharmacol 2008;65(6):833-840. PubMed
- Thomas, J. E., Munir, J. A., McIntyre, P. Z., and Ferguson, M. A. STEMI in a 24-year-old man after use of a synephrine-containing dietary supplement: a case report and review of the literature. Tex.Heart Inst.J 2009;36(6):586-590.
- Campbell-Tofte, J. I., Molgaard, P., Josefsen, K., Abdallah, Z., Hansen, S. H., Cornett, C., Mu, H., Richter, E. A., Petersen, H. W., Norregaard, J. C., and Winther, K. Randomized and double-blinded pilot clinical study of the safety and anti-diabetic ef
- Seifert, J. G., Nelson, A., Devonish, J., Burke, E. R., and Stohs, S. J. Effect of acute administration of an herbal preparation on blood pressure and heart rate in humans. Int J Med Sci 2011;8(3):192-197. PubMed
- Stohs, S. J., Preuss, H. G., Keith, S. C., Keith, P. L., Miller, H., and Kaats, G. R. Effects of p-synephrine alone and in combination with selected bioflavonoids on resting metabolism, blood pressure, heart rate and self-reported mood changes. Int J Med
- Wason, S., DiGiacinto, J. L., and Davis, M. W. Effects of grapefruit and Seville orange juices on the pharmacokinetic properties of colchicine in healthy subjects. Clin Ther 2012;34(10):2161-2173. PubMed
- Kaats, G. R., Miller, H., Preuss, H. G., and Stohs, S. J. A 60day double-blind, placebo-controlled safety study involving Citrus aurantium (bitter orange) extract. Food Chem Toxicol. 2013;55:358-362.
- Calapai, G., Firenzuoli, F., Saitta, A., Squadrito, F. R., Arlotta, M., Costantino, G., and Inferrera, G. Antiobesity and cardiovascular toxic effects of Citrus aurantium extracts in the rat: a preliminary report. Fitoterapia 12-1-1999;70(6):586-592. DOI
- Colker, C., Kalman, D., and Torina, G. Effects of Citrus aurantium extract, caffeine, and St. John's Wort on body fat loss, lipid levels, and mood states in overweight healthy adults. Curr Ther Res 1999;60:145-153. DOI
- Shara M, Stohs SJ. Safety evaluation of Bitter orange extract (p-synephrine) in healthy volunteers. J.Amer.Coll.Nutr. 2011;30:358.
- Lynch B. Review of the safety of p-synephrine and caffeine. Intertek-Cantox Report, 2013;1-20.
- Smith TB, Staub BA, Natarajan GM, et al. Acute myocardial infarction associated with dietary supplements containing 1,3-dimethylamylamine and Citrus aurantium. Tex Heart Inst J 2014;41(1):70-2. PubMed
- Shara M, Stohs SJ, Mukattash TL. Cardiovascular safety of oral p-synephrine (bitter orange) in healthy subjects: a randomized placebo-controlled cross-over clinical trial. Phytother Res. 2016;30(5):842-7.
- Liu Y, Santillo MF. Cytochrome P450 2D6 and 3A4 enzyme inhibition by amine stimulants in dietary supplements. Drug Test Anal. 2016;8(3-4):307-10. PubMed
- Abdelkawy KS, Donia AM, Turner RB, Elbarbry F. Effects of Lemon and Seville Orange Juices on the Pharmacokinetic Properties of Sildenafil in Healthy Subjects. Drugs R D. 2016 Sep;16(3):271-278. PubMed
- Gutiérrez-Hellín J, Salinero JJ, Abían-Vicen J, Areces F, Lara B, Gallo C, et al. Acute consumption of p-synephrine does not enhance performance in sprint athletes.J. Appl Physiol Nutr Metab. 2016;41(1):63-9. doi: 10.1139/apnm-2015-0299.
- Jung YP, Earnest CP, Koozehchian M, et al. Effects of ingesting a pre-workout dietary supplement with and without synephrine for 8 weeks on training adaptations in resistance-trained males. J Int Soc Sports Nutr. 2017;3;14:1. doi: 10.1186/s12970-016-0158- PubMed
- Jung YP, Earnest CP, Koozehchian M, et al. Effects of acute ingestion of a pre-workout dietary supplement with and without synephrine on resting energy expenditure, cognitive function and exercise performance. J Int Soc Sports Nutr. 2017;14:3. doi: 10.118
- Vatsavai LK, Kilari EK. Interaction of p-synephrine on the pharmacodynamic and pharmacokinetics of gliclazide in animal models. J Ayurveda Integr Med 2017; S0975-9476(16)30487-9. doi: 10.1016/j.jaim.2017.04.010.
- Ratamess NA, Bush JA, Stohs SJ, et al. Acute cardiovascular effects of bitter orange extract (p-synephrine) consumed alone and in combination with caffeine in human subjects: A placebo-controlled, double-blind study. Phytother Res. 2018;32(1):94-102.
- Gutiérrez-Hellín J, Ruiz-Moreno C, Del Coso J. Acute p-synephrine ingestion increases whole-body fat oxidation during 1-h of cycling at Fatmax. Eur J Nutr. 2019 Nov 5. PubMed
- Karimzadeh Z, Azizzadeh Forouzi M, Tajadini H, Ahmadinejad M, Roy C, Dehghan M. Effects of lavender and Citrus aurantium on pain of conscious intensive care unit patients: a parallel randomized placebo-controlled trial. J Integr Med 2021:S2095-4964(21)000 PubMed
- Koncz D, Tóth B, Bahar MA, Roza O, Csupor D. The Safety and Efficacy of Citrus aurantium (Bitter Orange) Extracts and p-Synephrine: A Systematic Review and Meta-Analysis. Nutrients 2022;14(19):4019. PubMed
Grape 34 references
- Kiesewetter H, Koscielny J, Kalus U, et al. Efficacy of orally administered extract of red vine leaf AS 195 (folia vitis viniferae) in chronic venous insufficiency (stages I-II). A randomized, double-blind, placebo-controlled trial. Arzneimittelforschung
- Xiao Dong S, Zhi Ping Z, Zhong Xiao W, et al. Possible enhancement of the first-pass metabolism of phenacetin by ingestion of grape juice in Chinese subjects. Br J Clin Pharmacol 1999;48:638-40. PubMed
- Vaswani SK, Hamilton RG, Carey RN, et al. Anaphylaxis recurrent urticaria and angioedema from grape hypersensitivity. J Allergy Clin Immunol 1998;101:S31.
- Chevallier A. The Encyclopedia of Medicinal Plants. London, UK: Dorling Kindersley, Ltd., 1996.
- Bernstein DI, Bernstein CK, Deng C, et al. Evaluation of the clinical efficacy and safety of grapeseed extract in the treatment of fall seasonal allergic rhinitis: a pilot study. Ann Allergy Asthma Immunol 2002;88:272-8.. PubMed
- Greenblatt DJ, von Moltke LL, Perloff ES, et al. Interaction of flurbiprofen with cranberry juice, grape juice, tea, and fluconazole: in vitro and clinical studies. Clin Pharmacol Ther 2006;79:125-33. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Ray, S. D., Parikh, H., Hickey, E., Bagchi, M., and Bagchi, D. Differential effects of IH636 grape seed proanthocyanidin extract and a DNA repair modulator 4-aminobenzamide on liver microsomal cytochrome 4502E1-dependent aniline hydroxylation. Mol Cell B PubMed
- O'Byrne, D. J., Devaraj, S., Grundy, S. M., and Jialal, I. Comparison of the antioxidant effects of Concord grape juice flavonoids alpha-tocopherol on markers of oxidative stress in healthy adults. Am J Clin.Nutr. 2002;76(6):1367-1374.
- Schaefer, E., Peil, H., Ambrosetti, L., and Petrini, O. Oedema protective properties of the red vine leaf extract AS 195 (Folia vitis viniferae) in the treatment of chronic venous insufficiency. A 6-week observational clinical trial. Arzneimittelforschun PubMed
- Nishikawa, M., Ariyoshi, N., Kotani, A., Ishii, I., Nakamura, H., Nakasa, H., Ida, M., Nakamura, H., Kimura, N., Kimura, M., Hasegawa, A., Kusu, F., Ohmori, S., Nakazawa, K., and Kitada, M. Effects of continuous ingestion of green tea or grape seed extra
- de Lange, D. W., Scholman, W. L., Kraaijenhagen, R. J., Akkerman, J. W., and van de Wiel, A. Alcohol and polyphenolic grape extract inhibit platelet adhesion in flowing blood. Eur.J Clin.Invest 2004;34(12):818-824. PubMed
- Samet, J. M. and Coultas, D. B. Reduced forced vital capacity in California grape workers. What does it mean? Am Rev.Respir.Dis 1992;145(2 Pt 1):255-256. PubMed
- Gamsky, T. E., McCurdy, S. A., Samuels, S. J., and Schenker, M. B. Reduced FVC among California grape workers. Am Rev.Respir.Dis 1992;145(2 Pt 1):257-262. PubMed
- de Lange, D. W., Verhoef, S., Gorter, G., Kraaijenhagen, R. J., van de Wiel, A., and Akkerman, J. W. Polyphenolic grape extract inhibits platelet activation through PECAM-1: an explanation for the French paradox. Alcohol Clin.Exp.Res 2007;31(8):1308-1314 PubMed
- Etheridge, A. S., Black, S. R., Patel, P. R., So, J., and Mathews, J. M. An in vitro evaluation of cytochrome P450 inhibition and P-glycoprotein interaction with goldenseal, Ginkgo biloba, grape seed, milk thistle, and ginseng extracts and their constitu
- Krikorian, R., Nash, T. A., Shidler, M. D., Shukitt-Hale, B., and Joseph, J. A. Concord grape juice supplementation improves memory function in older adults with mild cognitive impairment. Br J Nutr. 2010;103(5):730-734. PubMed
- Ingersoll, G. L., Wasilewski, A., Haller, M., Pandya, K., Bennett, J., He, H., Hoffmire, C., and Berry, C. Effect of concord grape juice on chemotherapy-induced nausea and vomiting: results of a pilot study. Oncol.Nurs.Forum 2010;37(2):213-221. PubMed
- Oliveira-Freitas, V. L., Dalla, Costa T., Manfro, R. C., Cruz, L. B., and Schwartsmann, G. Influence of purple grape juice in cyclosporine bioavailability. J Ren Nutr. 2010;20(5):309-313. PubMed
- Hollis, J. H., Houchins, J. A., Blumberg, J. B., and Mattes, R. D. Effects of concord grape juice on appetite, diet, body weight, lipid profile, and antioxidant status of adults. J Am Coll.Nutr. 2009;28(5):574-582. PubMed
- Dohadwala, M. M., Hamburg, N. M., Holbrook, M., Kim, B. H., Duess, M. A., Levit, A., Titas, M., Chung, W. B., Vincent, F. B., Caiano, T. L., Frame, A. A., Keaney, J. F., Jr., and Vita, J. A. Effects of Concord grape juice on ambulatory blood pressure in
- Rabe, E., Stucker, M., Esperester, A., Schafer, E., and Ottillinger, B. Efficacy and tolerability of a red-vine-leaf extract in patients suffering from chronic venous insufficiency--results of a double-blind placebo-controlled study. Eur.J Vasc.Endovasc. PubMed
- Trotta, M., Cesaretti, M., Conzi, R., Derchi, L. E., and Borgonovo, G. Elderly male with mesogastric pain. Small bowel obstruction caused by an intact fresh grape. Ann.Emerg.Med 2011;58(4):e1-e2. PubMed
- McCurdy, S. A., Wiggins, P., Schenker, M. B., Munn, S., Shaieb, A. M., Weinbaum, Z., Goldsmith, D., McGillis, S. T., Berman, B., and Samuels, S. Assessing dermatitis in epidemiologic studies: occupational skin disease among California grape and tomato ha
- Winter, C. K. and Kurtz, P. H. Factors influencing grape worker susceptibility to skin rashes. Bull.Environ.Contam Toxicol. 1985;35(3):418-426. PubMed
- Yamasaki, R., Dekio, S., and Jidoi, J. Contact dermatitis from grape bud. Contact Dermatitis 1985;12(4):226-227. PubMed
- Cox, J. and Grigg, M. Small bowel obstruction by an intact grape. J Am Geriatr.Soc 1986;34(7):550. PubMed
- Faircloth, D. E. and Robison, W. J. Obstruction of the sigmoid colon by grape seeds. JAMA 11-27-1981;246(21):2430. PubMed
- Marguerie, C. and Drouet, M. [Occupational eosinophilic lung in a grape grower: role of sulfites]. Allerg.Immunol.(Paris) 1995;27(5):163-167.
- Brito, FF., Martinez, A., Palacios, R., Mur, P., Gomez, E., Galindo, P. A., Borja, J., and Martinez, J. Rhinoconjunctivitis and asthma caused by vine pollen: a case report. J Allergy Clin Immunol 1999;103(2 Pt 1):262-266. PubMed
- Ras RT, Zock PL, Zebregs YE, et al. Effect of polyphenol-rich grape seed extract on ambulatory blood pressure in subjects with pre- and stage I hypertension. Br J Nutr 2013;110(12):2234-41. PubMed
- Berry AC, Nakshabendi R, Abidali H, et al. Adverse effects of grape seed extract supplement: A clinical case and long-term follow-up. J Diet Suppl. 2016;13(2):232-5. PubMed
- Martínez-Maqueda D, Zapatera B, Gallego-Narbón A, Vaquero MP, Saura-Calixto F, Pérez-Jiménez J. A 6-week supplementation with grape pomace to subjects at cardiometabolic risk ameliorates insulin sensitivity, without affecting other metabolic syndrome mark
- Moon SW, Shin YU, Cho H, Bae SH, Kim HK; and for the Mogen Study Group. Effect of grape seed proanthocyanidin extract on hard exudates in patients with non-proliferative diabetic retinopathy. Medicine (Baltimore) 2019;98(21):e15515. PubMed
Alpha-gpc 4 references
- Di Perri R, Coppola G, Ambrosio LA, et al. A multicentre trial to the evaluate the efficacy and tolerability of alpha-glycerylphosphorylcholine versus cytosine diphosphocholine in patients with vascular dementia. J Int Med Res 1991;19:330-41.
- Barbagallo Sangiorgi G, Barbagallo M, Giordano M, et al. Alpha-glycerophosphocholine in the mental recovery of cerebral ischemic attacks: An Italian multicenter clinical trial. Ann N Y Acad Sci 1994;717:253-69. PubMed
- Canal N, Franceschi M, Alberoni M, et al. Effect of L-alpha-glyceryl-phosphorylcholine on amnesia caused by scopolamine. Int J Clin Pharmacol Ther Toxicol 1991;29:103-7.
- Lee G, Choi S, Chang J, et al. Association of L-a glycerylphosphorylcholine with subsequent stroke risk after 10 Years. JAMA Netw Open 2021;4(11):e2136008.
Yohimbe 66 references
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
- Milman N, Scheibel J, Jessen O. Lysine prophylaxis in recurrent herpes simplex labialis: a double-blind, controlled crossover study. Acta Derm Venereol 1980;60:85-7.
- Teloken C, Rhoden EL, Sogari P, et al. Therapeutic effects of high dose yohimbine hydrochloride on organic erectile dysfunction. J Urol 1998;159:122-4. PubMed
- Jacobsen FM. Fluoxetine-induced sexual dysfunction and an open trial of yohimbine. J Clin Psychiatry 1992;53:119-22.
- Hollander E, McCarley A. Yohimbine treatment of sexual side effects induced by serotonin reuptake blockers. J Clin Psychiatry 1992;53:207-9.
- Sandler B, Aronson P. Yohimbine-induced cutaneous drug eruption, progressive renal failure, and lupus-like syndrome. Urol 1993;41:343-5. PubMed
- Kearney T, Tu N, Haller C. Adverse drug events associated with yohimbine-containing products: a retrospective review of the California Poison Control System reported cases. Ann Pharmacother 2010;44:1022-9. PubMed
- VandenBrink, B. M., Foti, R. S., Rock, D. A., Wienkers, L. C., and Wahlstrom, J. L. Prediction of CYP2D6 drug interactions from in vitro data: evidence for substrate-dependent inhibition. Drug Metab Dispos. 2012;40(1):47-53. PubMed
- Abebe, W. An overview of herbal supplement utilization with particular emphasis on possible interactions with dental drugs and oral manifestations. J Dent.Hyg. 2003;77(1):37-46.
- Mustonen, P., Savola, J., and Lassila, R. Atipamezole, an imidazoline-type alpha(2)-adrenoceptor inhibitor, binds to human platelets and inhibits their adrenaline-induced aggregation more effectively than yohimbine. Thromb.Res 8-1-2000;99(3):231-237.
- Cameron, O. G., Zubieta, J. K., Grunhaus, L., and Minoshima, S. Effects of yohimbine on cerebral blood flow, symptoms, and physiological functions in humans. Psychosom.Med 2000;62(4):549-559. PubMed
- Bowes, M. P., Peters, R. H., Kernan, W. J., Jr., and Hopper, D. L. Effects of yohimbine and idazoxan on motor behaviors in male rats. Pharmacol.Biochem.Behav. 1992;41(4):707-713.
- Bagheri, H., Schmitt, L., Berlan, M., and Montastruc, J. L. Effect of 3 weeks treatment with yohimbine on salivary secretion in healthy volunteers and in depressed patients treated with tricyclic antidepressants. Br J Clin Pharmacol 1992;34(6):555-558. PubMed
- Bagheri, H., Bompart, G., Girolami, J. P., Montastruc, J. L., and Montastruc, P. Is yohimbine-induced increase in salivary secretion a kinin-dependent mechanism? Fundam.Clin Pharmacol 1992;6(1):17-20. PubMed
- Swann, A. C., Birnbaum, D., Jagar, A. A., Dougherty, D. M., and Moeller, F. G. Acute yohimbine increases laboratory-measured impulsivity in normal subjects. Biol.Psychiatry 5-15-2005;57(10):1209-1211. PubMed
- Adeniyi, A. A., Brindley, G. S., Pryor, J. P., and Ralph, D. J. Yohimbine in the treatment of orgasmic dysfunction. Asian J Androl 2007;9(3):403-407. PubMed
- Murburg, M. M., Villacres, E. C., Ko, G. N., and Veith, R. C. Effects of yohimbine on human sympathetic nervous system function. J Clin Endocrinol.Metab 1991;73(4):861-865. PubMed
- Giampreti, A., Lonati, D., Locatelli, C., Rocchi, L., and Campailla, M. T. Acute neurotoxicity after yohimbine ingestion by a body builder. Clin Toxicol.(Phila) 2009;47(8):827-829. PubMed
- Bloomer, R. J., Canale, R. E., Blankenship, M. M., Hammond, K. G., Fisher-Wellman, K. H., and Schilling, B. K. Effect of the dietary supplement Meltdown on catecholamine secretion, markers of lipolysis, and metabolic rate in men and women: a randomized,
- Myers, A. and Barrueto, F., Jr. Refractory priapism associated with ingestion of yohimbe extract. J Med Toxicol. 2009;5(4):223-225.
- Berlin, I., Crespo-Laumonnier, B., Cournot, A., Landault, C., Aubin, F., Legrand, J. C., and Puech, A. J. The alpha 2-adrenergic receptor antagonist yohimbine inhibits epinephrine-induced platelet aggregation in healthy subjects. Clin Pharmacol.Ther. 199
- Swann, A. C. Mechanisms of impulsivity in bipolar disorder and related illness. Epidemiol.Psichiatr.Soc. 2010;19(2):120-130.
- Shibao, C., Okamoto, L. E., Gamboa, A., Yu, C., Diedrich, A., Raj, S. R., Robertson, D., and Biaggioni, I. Comparative efficacy of yohimbine against pyridostigmine for the treatment of orthostatic hypotension in autonomic failure. Hypertension 2010;56(5) PubMed
- Soeter, M. and Kindt, M. Stimulation of the noradrenergic system during memory formation impairs extinction learning but not the disruption of reconsolidation. Neuropsychopharmacology 2012;37(5):1204-1215. PubMed
- Cimolai, N. and Cimolai, T. Yohimbine use for physical enhancement and its potential toxicity. J Diet.Suppl 2011;8(4):346-354. PubMed
- Bagheri, H., Berlan, M., Montastruc, J. L., and Montastruc, P. Yohimbine and lacrimal secretion. Br J Clin Pharmacol. 1990;30(1):151-152.
- Landis, E. and Shore, E. Yohimbine-induced bronchospasm. Chest 1989;96(6):1424. PubMed
- Susset, J. G., Tessier, C. D., Wincze, J., Bansal, S., Malhotra, C., and Schwacha, M. G. Effect of yohimbine hydrochloride on erectile impotence: a double-blind study. J Urol. 1989;141(6):1360-1363. PubMed
- Chatelut, E., Rispail, Y., Berlan, M., and Montastruc, J. L. Yohimbine increases human salivary secretion. Br.J Clin Pharmacol. 1989;28(3):366-368. PubMed
- Montastruc, P., Berlan, M., and Montastruc, J. L. Effects of yohimbine on submaxillary salivation in dogs. Br J Pharmacol 1989;98(1):101-104. PubMed
- Charney, D. S., Price, L. H., and Heninger, G. R. Desipramine-yohimbine combination treatment of refractory depression. Implications for the beta-adrenergic receptor hypothesis of antidepressant action. Arch.Gen.Psychiatry 1986;43(12):1155-1161. PubMed
- Braddock, L., Cowen, P. J., Elliott, J. M., Fraser, S., and Stump, K. Binding of yohimbine and imipramine to platelets in depressive illness. Psychol.Med 1986;16(4):765-773. PubMed
- Bolme, P., Corrodi, H., Fuxe, K., Hokfelt, T., Lidbrink, P., and Goldstein, M. Possible involvement of central adrenaline neurons in vasomotor and respiratory control. Studies with clonidine and its interactions with piperoxane and yohimbine. Eur J Pharm PubMed
- Charney, D. S., Heninger, G. R., and Sternberg, D. E. Assessment of alpha 2 adrenergic autoreceptor function in humans: effects of oral yohimbine. Life Sci 6-7-1982;30(23):2033-2041.
- Boon, N. A., Elliott, J. M., Grahame-Smith, D. G., John-Green, T., and Stump, K. A comparison of alpha 2-adrenoreceptor binding characteristics of intact human platelets identified by [3H]-yohimbine and [3H]- dihydroergocryptine. J Auton.Pharmacol 1983;3
- Andrejak, M., Ward, M., and Schmitt, H. Cardiovascular effects of yohimbine in anaesthetized dogs. Eur.J Pharmacol 10-28-1983;94(3-4):219-228. PubMed
- Brodde, O. E., Anlauf, M., Arroyo, J., Wagner, R., Weber, F., and Buck, K. D. Hypersensitivity of adrenergic receptors and blood-pressure response to oral yohimbine in orthostatic hypotension. N.Engl.J Med 4-28-1983;308(17):1033-1034. PubMed
- Charney, D. S., Heninger, G. R., and Redmond, D. E., Jr. Yohimbine induced anxiety and increased noradrenergic function in humans: effects of diazepam and clonidine. Life Sci. 7-4-1983;33(1):19-29. PubMed
- Knoll, L. D., Benson, R. C., Jr., Bilhartz, D. L., Minich, P. J., and Furlow, W. L. A randomized crossover study using yohimbine and isoxsuprine versus pentoxifylline in the management of vasculogenic impotence. J Urol. 1996;155(1):144-146. DOI
- Betz, J. M., White, K. D., and der Marderosian, A. H. Gas chromatographic determination of yohimbine in commercial yohimbe products. J AOAC Int 1995;78(5):1189-1194. DOI
- Bagheri, H., Chale, J. J., Guyen, L. N., Tran, M. A., Berlan, M., and Montastruc, J. L. Evidence for activation of both adrenergic and cholinergic nervous pathways by yohimbine, an alpha 2-adrenoceptor antagonist. Fundam.Clin Pharmacol 1995;9(3):248-254.
- Kennedy, S. H., Gnam, W., Ralevski, E., and Brown, G. M. Melatonin responses to clonidine and yohimbine challenges. J Psychiatry Neurosci. 1995;20(4):297-304.
- Musso, N. R., Vergassola, C., Pende, A., and Lotti, G. Yohimbine effects on blood pressure and plasma catecholamines in human hypertension. Am J Hypertens. 1995;8(6):565-571. PubMed
- Morgan, C. A., III, Southwick, S. M., Grillon, C., Davis, M., Krystal, J. H., and Charney, D. S. Yohimbine-facilitated acoustic startle reflex in humans. Psychopharmacology (Berl) 1993;110(3):342-346. PubMed
- Adler, L. E., Hoffer, L., Nagamoto, H. T., Waldo, M. C., Kisley, M. A., and Giffith, J. M. Yohimbine impairs P50 auditory sensory gating in normal subjects. Neuropsychopharmacology 1994;10(4):249-257. PubMed
- Biaggioni, I., Robertson, R. M., and Robertson, D. Manipulation of norepinephrine metabolism with yohimbine in the treatment of autonomic failure. J Clin Pharmacol. 1994;34(5):418-423. PubMed
- Kenney, W. L., Zappe, D. H., Tankersley, C. G., and Derr, J. A. Effect of systemic yohimbine on the control of skin blood flow during local heating and dynamic exercise. Am J Physiol 1994;266(2 Pt 2):H371-H376. PubMed
- Friesen, K., Palatnick, W., and Tenenbein, M. Benign course after massive ingestion of yohimbine. J Emerg.Med 1993;11(3):287-288. PubMed
- Bierer, L. M., Aisen, P. S., Davidson, M., Ryan, T. M., Stern, R. G., Schmeidler, J., and Davis, K. L. A pilot study of oral physostigmine plus yohimbine in patients with Alzheimer disease. Alzheimer Dis.Assoc.Disord. 1993;7(2):98-104. PubMed
- Mann, K., Klingler, T., Noe, S., Roschke, J., Muller, S., and Benkert, O. Effects of yohimbine on sexual experiences and nocturnal penile tumescence and rigidity in erectile dysfunction. Arch.Sex Behav. 1996;25(1):1-16. PubMed
- Rowland, D. L., Kallan, K., and Slob, A. K. Yohimbine, erectile capacity, and sexual response in men. Arch Sex Behav 1997;26(1):49-62.
- Bremner, J. D., Innis, R. B., Ng, C. K., Staib, L. H., Salomon, R. M., Bronen, R. A., Duncan, J., Southwick, S. M., Krystal, J. H., Rich, D., Zubal, G., Dey, H., Soufer, R., and Charney, D. S. Positron emission tomography measurement of cerebral metaboli
- Riley AJ, Goodman R, Kellett JM, and et al. Double blind trial of yohimbine hydrochloride in the treatment of erection inadequacy. Sexual Marital Ther 1989;4(1):17-26. DOI
- Cohen PA, Wang YH, Maller G, DeSouza R, Khan IA. Pharmaceutical quantities of yohimbine found in dietary supplements in the USA. Drug Test Anal. 2015 Sep 22. PubMed
- Ruck B, Shih RD, Marcus SM. Hypertensive crisis from herbal treatment of impotence. Am J Emerg Med. 1999;17:317-318. PubMed
- Wylie KR. Yohimbine and sinusitis. Br J Psychiatry. 1996;169(3):384-5. PubMed
- Le Corre P, Parmer RJ, Kailasam MT, et al. Human sympathetic activation by alpha2-adrenergic blockade with yohimbine: Bimodal, epistatic influence of cytochrome P450-mediated drug metabolism. Clin Pharmacol Ther. 2004;76(2):139-53.
- Mueller-Schoell A, Michelet R, Weinelt F, Kloft C, Mikus G. CYP2D6 phenotype explains reported yohimbine concentrations in four severe acute intoxications. Arch Toxicol. 2021. PubMed
- Bharucha AE, Skaar T, Andrews CN, et al Relationship of cytochrome P450 pharmacogenetics to the effects of yohimbine on gastrointestinal transit and catecholamines in healthy subjects. Neurogastroenterol Motil. 2008;20(8):891-9. PubMed
- Schmauss M, Laakmann G, Dieterle D. Effects of alpha 2-receptor blockade in addition to tricyclic antidepressants in therapy-resistant depression. J Clin Psychopharmacol. 1988;8(2):108-11.
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Hodapp B, Haggerty A, Feldman R, Timpe J. Intracranial hemorrhage after a single dose of Yohimbine in a chronic user of clonidine. Am J Emerg Med 2022;62:145. PubMed
- Vay M, Meyer MJ, Blank A, et al. Oral yohimbine as a new probe drug to predict CYP2D6 activity: results of a fixed-sequence phase I trial. Clin Pharmacokinet. 2020;59(7):927-939. PubMed
Cowhage 12 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Anon. Epidemiological notes and reports: Mucuna pruriens-associated pruritus--New Jersey. MMWR Morb Mortal Wkly Rep 1985;34:732-3.
- HP-200 in Parkinson's Disease study group. An alternative medicine treatment for Parkinson's disease: Results of a multicenter clinical trial. J Alt Comp Med 1995;1:249-55. DOI
- Infante ME, Perez AM, Simao MR, et al. Outbreak of acute toxic psychosis attributed to Mucuna pruriens. Lancet 1990;336:1129. PubMed
- Vaidya AB, Rajagopalan TG, Mankodi NA, et al. Treatment of Parkinson's disease with the cowhage plant-Mucuna pruriens Bak. Neurol India 1978;26:171-6.
- Vadivel V, Janardhanan K. Nutritional and anti-nutritional composition of velvet bean: an under-utilized food legume in south India. Int J Food Sci Nutr 2000;51:279-87. PubMed
- Akhtar MS, Qureshi AQ, Iqbal J. Antidiabetic evaluation of Mucuna pruriens, Linn seeds. J Pak Med Assoc 1990;40:147-50.
- Prakash, D., Niranjan, A., and Tewari, S. K. Some nutritional properties of the seeds of three Mucuna species. Int.J.Food Sci.Nutr. 2001;52(1):79-82.
- Vadivel, V. and Janardhanan, K. Nutritional and antinutritional characteristics of seven South Indian wild legumes. Plant Foods Hum.Nutr 2005;60(2):69-75. PubMed
- Creapure (Creatine Monohydrate). Toxicological Datasheet. Degussa BioActives. Available at: https://www.fda.gov/ohrms/DOCKETS/.../95s-0316-rpt0154-54-Ref-50-vol112.pdf.
- Pulikkalpura H, Kurup R, Mathew PJ, Baby S. Levodopa in Mucuna pruriens and its degradation. Sci Rep 2015;5:11078. PubMed
N-methyltyramine 2 references
- Pawar RS, Grundel E. Overview of regulation of dietary supplements in the USA and issues of adulteration with phenethylamines (PEAs). Drug Test Anal 2017;9:500-517. PubMed
- Stohs SJ, Hartman MJ. A review of the receptor binding and pharmacological effects of N-methyltyramine. Phytother Res. 2015;29(1):14-6.
Phenethylamine (pea) 9 references
- Singhal AB, Caviness VS, Begleiter AF, et al. Cerebral vasoconstriction and stroke after use of serotonergic drugs. Neurology 2002;58:130-3. PubMed
- Sabelli H, Fink P, Fawcett J, et al. Sustained antidepressant effect of PEA replacement. J Neuropsychiatry Clin Neurosci. 1996;8(2):168-71.
- Xie Z, Miller G. Beta-phenylehtylamine alters monoamine transporter function via trace amine-associated receptor 1: implication for modulatory roles of trace amines in brain. J Pharmacol Exp Ther. 2008;325(2):617-28.
- Lukasik-Glebocka M, Sommerfeld K, Tezyk A, et al. [Acute poisoning with weight-loss dietary supplement falsely suggesting the use of amphetamine]. Przegl Lek. 2013;70(10):880-3.
- Nakamura M, Ishii A, Nakahara D. Characterization of beta-phenyltheylamine-induced monoamine release in rat nucleus accumbens: a microdialysis study. Eur J Pharmacol. 1998;349(2-3):163-9.
- Bailey B, Philips S, Boulton A. In vivo release of endogenous dopamine, 5-hydroxytryptamine and some of their metabolites from rat caudate nucleus by phenylethylamine. Neurochem Res. 1987;12(2):173-8. PubMed
- Mantegazza P, Riva M. Amphetamine-like activity of beta-phenethylamine after a monoamine oxidase inhibitor in vivo. Journal of Pharmacy and Pharmacology. 1963;151(1):472-8.
- Grimsby J, Toth M, Chen K, et al. Increased stress response and beta-phenylethylamine in MAOB-deficient mice. Nat Genet. 1997;17(2):206-10.
- Lindemann L, Hoener MC. A renaissance in trace amines inspired by a novel GPCR family. Trends Pharmacol Sci. 2005;26(5):274-81. PubMed
See these in context on the Phenethylamine (pea) monograph →
Methylsynephrine 3 references
- Pawar RS, Grundel E. Overview of regulation of dietary supplements in the USA and issues of adulteration with phenethylamines (PEAs). Drug Test Anal 2017;9:500-517. PubMed
- Cohen PA, Avula B, Venhuis B, Travis JC, Wang YH, Khan IA. Pharmaceutical doses of the banned stimulant oxilofrine found in dietary supplements sold in the USA. Drug Test Anal. 2017;9(1):135-142. PubMed
- Venhuis B, Keizers P, van Riel A, de Kaste D. A cocktail of synthetic stimulants found in a dietary supplement associated with serious adverse events. Drug Test Anal. 2014;6(6):578-81. PubMed
Deanol 15 references
- Davies C, Maidment S, Hanley P, et al. Dimethylaminoethanol (DMAE). HSE. Risk assessment document; EH72/2;1997. (TOXLINE).
- Re O. 2-Dimethylaminoethanol (deanol): a brief review of its clinical efficacy and postulated mechanism of action. Curr Ther Res Clin Exp 1974;16:1238-42.
- Pieralisi G, Ripari P, Vecchiet L. Effects of a standardized ginseng extract combined with dimethylaminoethanol bitartrate, vitamins, minerals, and trace elements on physical performance during exercise. Clin Ther 1991;13:373-82.
- George J, Pridmore S, Aldous D. Double blind controlled trial of deanol in tardive dyskinesia. Aust N Z J Psychiatry 1981;15:68-71. PubMed
- Penovich P, Morgan JP, Kerzner B, et al. Double-blind evaluation of deanol in tardive dyskinesia. JAMA 1978;239:1997-8. DOI
- de Montigny C, Chouinard G, Annable L. Ineffectiveness of deanol in tardive dyskinesia: a placebo controlled study. Psychopharmacology (Berl) 1979;65:219-23. PubMed
- Lindeboom SF, Lakke JP. Deanol and physostigmine in the treatment of L-dopa-induced dyskinesias. Acta Neurol Scand 1978;58:134-8. PubMed
- Jus A, Villeneuve A, Gautier J, et al. Deanol, lithium and placebo in the treatment of tardive dyskinesia. A double-blind crossover study. Neuropsychobiology 1978;4:140-9. PubMed
- Lewis JA, Young R. Deanol and methylphenidate in minimal brain dysfunction. Clin Pharmacol Ther 1975;17:534-40. PubMed
- Fisman M, Mersky H, Helmes E. Double-blind trial of 2-dimethylaminoethanol in Alzheimer's disease. Am J Psychiatry 1981;138:970-2. PubMed
- Ferris SH, Sathananthan G, Gershon S, et al. Senile dementia: treatment with deanol. J Am Geriatr Soc 1977;25:241-4. PubMed
- Haug BA, Holzgraefe M. Orofacial and respiratory tardive dyskinesia: potential side effects of 2-dimethylaminoethanol (deanol)? Eur Neurol 1991;31:423-5. PubMed
- Casey DE. Mood alterations during deanol therapy. Psychopharmacology (Berl) 1979;62:187-91. PubMed
- Sergio W. Use of DMAE (2-dimethylaminoethanol) in the induction of lucid dreams. Med Hypotheses 1988;26:255-7. PubMed
- Osol A, Hoover JE, eds. Remington's Pharmaceutical Science, 15th ed. Easton, PA: Mack Publishing Company, 1975.
Isopropylnorsynephrine 3 references
- Venhuis B, Keizers P, van Riel A, de Kaste D. A cocktail of synthetic stimulants found in a dietary supplement associated with serious adverse events. Drug Test Anal. 2014 Jun;6(6):578-81. doi: 10.1002/dta.1664. Epub 2014 May 6. PubMed
- Cohen PA, Travis JC, Vanhee C, Ohana D, Venhuis BJ. Nine prohibited stimulants found in sports and weight loss supplements: deterenol, phenpromethamine (Vonedrine), oxilofrine, octodrine, beta-methylphenylethylamine (BMPEA), 1,3-dimethylamylamine (1,3-DMA
- Anderson WG. The sympathomimetic activity of N-isopropyloctopamine in vitro. J Pharmacol Exp Ther 1983;225(3):553-8. DOI
See these in context on the Isopropylnorsynephrine monograph →
Hordenine 3 references
- Barwell CJ, Basma AN, Lafi MA, Leake LD. Deamination of hordenine by monoamine oxidase and its action on vasa deferentia of the rat. J Pharm Pharmacol 1989;41(6):421-3. PubMed
- Nelson BC, Putzbach K, Sharpless KE, Sander LC. Mass spectrometric determination of the predominant adrenergic protoalkaloids in bitter orange (Citrus aurantium). J Agric Food Chem 2007;55(24):9769-75. PubMed
- Liu Y, Santillo MF. Cytochrome P450 2D6 and 3A4 enzyme inhibition by amine stimulants in dietary supplements. Drug Test Anal. 2016;8(3-4):307-10. PubMed
Capsicum 89 references
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Cooper RL, Cooper MM. Red pepper-induced dermatitis in breast-fed infants. Dermatol 1996;93:61-2. PubMed
- Millqvist E. Cough provocation with capsaicin is an objective way to test sensory hyperreactivity in patients with asthma-like symptoms. Allergy 2000;55:546-50. DOI
- Locock RA. Capsicum. Can Pharm J 1985;118:517-9.
- Mason L, Moore RA, Derry S, et al. Systematic review of topical capsaicin for the treatment of chronic pain. BMJ 2004;328:991. PubMed
- Schmulson MJ, Valdovinos MA, Milke P. Chili pepper and rectal hyperalgesia in irritable bowel syndrome. Am J Gastroenterol 2003;98:1214-5. PubMed
- Surh YJ, Lee SS. Capsaicin in hot chili pepper: carcinogen, co-carcinogen or anticarcinogen? Food Chem Toxicol 1996;34:313-6. PubMed
- Bouraoui A, Brazier JL, Zouaghi H, Rousseau M. Theophylline pharmacokinetics and metabolism in rabbits following single and repeated administration of Capsicum fruit. Eur J Drug Metab Pharmacokinet 1995;20:173-8.
- Hogaboam CM, Wallace JL. Inhibition of platelet aggregation by capsaicin. An effect unrelated to actions on sensory afferent neurons. Eur J Pharmacol 1991;202:129-31. PubMed
- Wang JP, Hsu MF, Teng CM. Antiplatelet effect of capsaicin. Thromb Res 1984;36:497-507. PubMed
- Williams SR, Clark RF, Dunford JV. Contact dermatitis associated with capsaicin: Hunan hand syndrome. Ann Emerg Med 1995;25:713-5. PubMed
- Zollman TM, Bragg RM, Harrison DA. Clinical effects of oleoresin capsicum (pepper spray) on the human cornea and conjunctiva. Ophthalmology 2000;107:2186-9. PubMed
- Bortolotti M, Coccia G, Grossi G, Miglioli M. The treatment of functional dyspepsia with red pepper. Aliment Pharmacol Ther 2002;16:1075-82. PubMed
- Hakas JF Jr. Topical capsaicin induces cough in patient receiving ACE inhibitor. Ann Allergy 1990;65:322-3.
- Rapoport AM, Bigal ME, Tepper SJ, Sheftell FD. Intranasal medications for the treatment of migraine and cluster headache. CNS Drugs 2004;18:671-85. PubMed
- Stjarne P, Rinder J, Heden-Blomquist E, et al. Capsaicin desensitization of the nasal mucosa reduces symptoms upon allergen challenge in patients with allergic rhinitis. Acta Otolaryngol 1998;118:235-9. PubMed
- Levy RL. Intranasal capsaicin for acute abortive treatment of migraine without aura. Headache 1995;35:277.
- Fusco BM, Marabini S, Maggi CA, et al. Preventative effect of repeated nasal applications of capsaicin in cluster headache. Pain 1994;59:321-5. PubMed
- Sicuteri F, Fusco BM, Marabini S, et al. Beneficial effect of capsaicin application to the nasal mucosa in cluster headache. Clin J Pain 1989;5:49-53. PubMed
- Marabini S, Ciabatti PG, Polli G, et al. Beneficial effects of intranasal applications of capsaicin in patients with vasomotor rhinitis. Eur Arch Otorhinolaryngol 1991;248:191-4. PubMed
- Frerick H, Keitel W, Kuhn U, et al. Topical treatment of chronic low back pain with a capsicum plaster. Pain 2003;106:59-64. PubMed
- Keitel W, Frerick H, Kuhn U, et al. Capsicum pain plaster in chronic non-specific low back pain. Arzneimittelforschung 2001;51:896-903. PubMed
- Shalansky S, Lynd L, Richardson K, et al. Risk of warfarin-related bleeding events and supratherapeutic international normalized ratios associated with complementary and alternative medicine: a longitudinal analysis. Pharmacotherapy. 2007;27:1237-47. PubMed
- Sumano-López H, Gutiérrez-Olvera L, Aguilera-Jiménez R, et al. Administration of ciprofloxacin and capsaicin in rats to achieve higher maximal serum concentrations. Arzneimittelforschung. 2007;57(5):286-90. PubMed
- Wanwimolruk S, Nyika S, Kepple M, et al. Effects of capsaicin on the pharmacokinetics of antipyrine, theophylline and quinine in rats. J Pharm Pharmacol. 1993;45(7):618-21. PubMed
- Cruz L, Castañeda-Hernández G, Navarrete A. Ingestion of chilli pepper (Capsicum annuum) reduces salicylate bioavailability after oral asprin administration in the rat. Can J Physiol Pharmacol.
- Rodriguez-Stanley, S., Collings, K. L., Robinson, M., Owen, W., and Miner, P. B., Jr. The effects of capsaicin on reflux, gastric emptying and dyspepsia. Aliment.Pharmacol.Ther. 2000;14(1):129-134. PubMed
- Brown, L., Takeuchi, D., and Challoner, K. Corneal abrasions associated with pepper spray exposure. Am.J.Emerg.Med. 2000;18(3):271-272. PubMed
- Vesaluoma, M., Muller, L., Gallar, J., Lambiase, A., Moilanen, J., Hack, T., Belmonte, C., and Tervo, T. Effects of oleoresin capsicum pepper spray on human corneal morphology and sensitivity. Invest Ophthalmol.Vis.Sci. 2000;41(8):2138-2147.
- Stam, C., Bonnet, M. S., and van Haselen, R. A. The efficacy and safety of a homeopathic gel in the treatment of acute low back pain: a multi-centre, randomised, double-blind comparative clinical trial. Br Homeopath J 2001;90(1):21-28. PubMed
- Olajos, E. J. and Salem, H. Riot control agents: pharmacology, toxicology, biochemistry and chemistry. J.Appl.Toxicol. 2001;21(5):355-391. PubMed
- Fett, D. D. Botanical briefs: Capsicum peppers. Cutis 2003;72(1):21-23.
- McCarthy, G. M. and McCarty, D. J. Effect of topical capsaicin in the therapy of painful osteoarthritis of the hands. J.Rheumatol. 1992;19(4):604-607.
- Chaiyata, P., Puttadechakum, S., and Komindr, S. Effect of chili pepper (Capsicum frutescens) ingestion on plasma glucose response and metabolic rate in Thai women. J.Med.Assoc.Thai. 2003;86(9):854-860.
- Petruzzi, M., Lauritano, D., De Benedittis, M., Baldoni, M., and Serpico, R. Systemic capsaicin for burning mouth syndrome: short-term results of a pilot study. J.Oral Pathol.Med. 2004;33(2):111-114. PubMed
- Misra, M. N., Pullani, A. J., and Mohamed, Z. U. Prevention of PONV by acustimulation with capsicum plaster is comparable to ondansetron after middle ear surgery: [La prevention des NVPO par acustimulation avec un emplatre de Capsicum est comparable a ce PubMed
- Milke, P., Diaz, A., Valdovinos, M. A., and Moran, S. Gastroesophageal reflux in healthy subjects induced by two different species of chilli (Capsicum annum). Dig.Dis. 2006;24(1-2):184-188.
- de Jong, N. W., van der Steen, J. J., Smeekens, C. C., Blacquiere, T., Mulder, P. G., van Wijk, R. G., and de Groot, H. Honeybee interference as a novel aid to reduce pollen exposure and nasal symptoms among greenhouse workers allergic to sweet bell pepp
- Final report on the safety assessment of capsicum annuum extract, capsicum annuum fruit extract, capsicum annuum resin, capsicum annuum fruit powder, capsicum frutescens fruit, capsicum frutescens fruit extract, capsicum frutescens resin, and capsaicin.
- Tandan, R., Lewis, G. A., Krusinski, P. B., Badger, G. B., and Fries, T. J. Topical capsaicin in painful diabetic neuropathy. Controlled study with long-term follow-up. Diabetes Care 1992;15(1):8-14. PubMed
- Gupta, P. J. Red hot chilli consumption is harmful in patients operated for anal fissure - a randomized, double-blind, controlled study. Dig.Surg. 2007;24(5):354-357. PubMed
- Patane, S., Marte, F., Di Bella, G., Cerrito, M., and Coglitore, S. Capsaicin, arterial hypertensive crisis and acute myocardial infarction associated with high levels of thyroid stimulating hormone. Int.J Cardiol. 5-1-2009;134(1):130-132. PubMed
- Gupta, P. J. Consumption of red-hot chili pepper increases symptoms in patients with acute anal fissures. A prospective, randomized, placebo-controlled, double blind, crossover trial. Arq Gastroenterol. 2008;45(2):124-127. PubMed
- Gupta, P. J. Consumption of red-hot chili pepper increases symptoms in patients with acute anal fissures. Ann.Ital.Chir 2008;79(5):347-351.
- Patane, S., Marte, F., La Rosa, F. C., and La, Rocca R. Capsaicin and arterial hypertensive crisis. Int J Cardiol. 10-8-2010;144(2):e26-e27. PubMed
- Chaiyasit, K., Khovidhunkit, W., and Wittayalertpanya, S. Pharmacokinetic and the effect of capsaicin in Capsicum frutescens on decreasing plasma glucose level. J Med.Assoc.Thai. 2009;92(1):108-113.
- Blanc, P., Liu, D., Juarez, C., and Boushey, H. A. Cough in hot pepper workers. Chest 1991;99(1):27-32. PubMed
- Akcay, A. B., Ozcan, T., Seyis, S., and Acele, A. Coronary vasospasm and acute myocardial infarction induced by a topical capsaicin patch. Turk.Kardiyol.Dern.Ars 2009;37(7):497-500.
- van Boxel, O. S., ter Linde, J. J., Siersema, P. D., and Smout, A. J. Role of chemical stimulation of the duodenum in dyspeptic symptom generation. Am J Gastroenterol. 2010;105(4):803-811. PubMed
- Niemcunowicz-Janica, A., Ptaszynska-Sarosiek, I., and Wardaszka, Z. [Sudden death caused by an oleoresin capsicum spray]. Arch.Med.Sadowej.Kryminol. 2009;59(3):252-254.
- Reuter, J., Merfort, I., and Schempp, C. M. Botanicals in dermatology: an evidence-based review. Am J Clin Dermatol 2010;11(4):247-267. PubMed
- McCormack, P. L. Capsaicin dermal patch: in non-diabetic peripheral neuropathic pain. Drugs 10-1-2010;70(14):1831-1842. PubMed
- Bortolotti, M. and Porta, S. Effect of red pepper on symptoms of irritable bowel syndrome: preliminary study. Dig.Dis.Sci 2011;56(11):3288-3295. PubMed
- Webster, L. R., Peppin, J. F., Murphy, F. T., Lu, B., Tobias, J. K., and Vanhove, G. F. Efficacy, safety, and tolerability of NGX-4010, capsaicin 8% patch, in an open-label study of patients with peripheral neuropathic pain. Diabetes Res Clin Pract. 2011 PubMed
- Gerber, S., Frueh, B. E., and Tappeiner, C. Conjunctival proliferation after a mild pepper spray injury in a young child. Cornea 2011;30(9):1042-1044. PubMed
- Lim, L. G., Tay, H., and Ho, K. Y. Curry induces acid reflux and symptoms in gastroesophageal reflux disease. Dig.Dis.Sci 2011;56(12):3546-3550. PubMed
- Ludy, M. J., Moore, G. E., and Mattes, R. D. The effects of capsaicin and capsiate on energy balance: critical review and meta-analyses of studies in humans. Chem Senses 2012;37(2):103-121. PubMed
- Sayin, M. R., Karabag, T., Dogan, S. M., Akpinar, I., and Aydin, M. A case of acute myocardial infarction due to the use of cayenne pepper pills. Wien.Klin.Wochenschr. 2012;124(7-8):285-287. PubMed
- Bley, K., Boorman, G., Mohammad, B., McKenzie, D., and Babbar, S. A comprehensive review of the carcinogenic and anticarcinogenic potential of capsaicin. Toxicol.Pathol. 2012;40(6):847-873. PubMed
- Derry, S. and Moore, R. A. Topical capsaicin (low concentration) for chronic neuropathic pain in adults. Cochrane.Database.Syst.Rev. 2012;9:CD010111. PubMed
- Tominack, R. L. and Spyker, D. A. Capsicum and capsaicin--a review: case report of the use of hot peppers in child abuse. J.Toxicol.Clin.Toxicol. 1987;25(7):591-601. PubMed
- Schuurs, A. H., Abraham-Inpijn, L., van Straalen, J. P., and Sastrowijoto, S. H. An unusual case of black teeth. Oral Surg.Oral Med.Oral Pathol. 1987;64(4):427-431. PubMed
- Kumar, N., Vij, J. C., Sarin, S. K., and Anand, B. S. Do chillies influence healing of duodenal ulcer? Br.Med.J.(Clin.Res.Ed) 6-16-1984;288(6433):1803-1804. PubMed
- Steffee, C. H., Lantz, P. E., Flannagan, L. M., Thompson, R. L., and Jason, D. R. Oleoresin capsicum (pepper) spray and "in-custody deaths". Am.J.Forensic Med.Pathol. 1995;16(3):185-192. PubMed
- Knight, T. E. and Hayashi, T. Solar (brachioradial) pruritus--response to capsaicin cream. Int.J.Dermatol. 1994;33(3):206-209. DOI
- Watson, W. A., Stremel, K. R., and Westdorp, E. J. Oleoresin capsicum (Cap-Stun) toxicity from aerosol exposure. Ann.Pharmacother. 1996;30(7-8):733-735. PubMed
- Busker, R. W. and van Helden, H. P. Toxicologic evaluation of pepper spray as a possible weapon for the Dutch police force: risk assessment and efficacy. Am.J.Forensic Med.Pathol. 1998;19(4):309-316. PubMed
- Sausenthaler, S., Koletzko, S., Schaaf, B., Lehmann, I., Borte, M., Herbarth, O., von Berg, A., Wichmann, H. E., and Heinrich, J. Maternal diet during pregnancy in relation to eczema and allergic sensitization in the offspring at 2 y of age. Am J Clin Nu PubMed
- Bleuel I, Zinkernagel M, Tschopp M, Tappeiner C. Association of bilateral acute anterior uveitis with a capsaicin patch. Ocul Immunol Inflamm 2013;21(5):394-5. PubMed
- Casanueva B, Rodero B, Quintial C, Llorca J, González-Gay MA. Short-term efficacy of topical capsaicin therapy in severely affected fibromyalgia patients. Rheumatol Int 2013;33(10):2665-70. PubMed
- Copeland S, Nugent K. Persistent respiratory symptoms following prolonged capsaicin exposure. Int J Occup Environ Med. 2013;4(4):211-5.
- García-Menaya JM, Cordobés -Durán C, Bobadilla-González P, et al. Anaphylactic reaction to bell pepper (Capsicum annuum) in a patient with a latex-fruit syndrome. Allergol Immunopathol (Madr). 2014;42(3):263-5. PubMed
- Kim DH, Yoon KB, Park S, et al. Comparison of NSAID patch given as monotherapy and NSAID patch in combination with transcutaneous electric nerve stimulation, a heating pad, or topical capsaicin in the treatment of patients with myofascial pain syndrome o
- Kulkantrakorn K, Lorsuwansiri C, Meesawatsom P. 0.025% capsaicin gel for the treatment of painful diabetic neuropathy: a randomized, double-blind, crossover, placebo-controlled trial. Pain Pract. 2013;13(6):497-503. PubMed
- Pabalan N, Jarjanazi H, Ozcelik H. The impact of capsaicin intake on risk of developing gastric cancers: a meta-analysis. J Gastrointest Cancer. 2014;45(3):334-41. PubMed
- Sandor B, Papp J, Mozsik G, et al. Orally given gastroprotective capsaicin does not modify aspirin-induced platelet aggregation in healthy male volunteers (human phase I examination). Acta Physiol Hung. 2014 Dec;101(4):429-37. PubMed
- Van Nooten F, Treur M, Pantiri K, Stoker M, Charokopou M. Capsaicin 8% patch versus oral neuropathic pain medications for the treatment of painful diabetic peripheral neuropathy: a systematic literature review and network meta-analysis. Clin Ther. 2017 Ap PubMed
- Simpson DM, Robinson-Papp J, Van J, et al. Capsaicin 8% patch in painful diabetic peripheral neuropathy: a randomized, double-blind, placebo-controlled study. J Pain. 2017 Jan;18(1):42-53. PubMed
- Campbell CM, Diamond E, Schmidt WK, et al. A randomized, double-blind, placebo-controlled trial of injected capsaicin for pain in Morton's neuroma. Pain. 2016 Jun;157(6):1297-304. PubMed
- Jorgensen MR, Pedersen AM. Analgesic effect of topical oral capsaicin gel in burning mouth syndrome. Acta Odontol Scand. 2017 Mar;75(2):130-6.
- Yuan LJ, Qin Y, Wang L, et al. Capsaicin-containing chili improved postprandial hyperglycemia, hyperinsulinemia, and fasting lipid disorders in women with gestational diabetes mellitus and lowered the incidence of large-for-gestational-age newborns. Clin PubMed
- Dean DJ, Sabagha N, Rose K, et al. A pilot trial of topical capsaicin cream for treatment of cannabinoid hyperemesis syndrome. Acad Emerg Med. 2020;27(11):1166-1172. PubMed
- Jang HH, Lee J, Lee SH, Lee YM. Effects of Capsicum annuum supplementation on the components of metabolic syndrome: a systematic review and meta-analysis. Sci Rep. 2020;10(1):20912. PubMed
- Joseph MSc A, John PhD F, Thomas MSc JV, Sivadasan SDP, Maliakel PhD B, Mohan PhD R, I M K. Influence of a novel food-grade formulation of red chili extract (Capsicum annum) on overweight subjects: Randomized, double-blinded, placebo-controlled study. J D
- Kocak AO, Dogruyol S, Akbas I, et al. Comparison of topical capsaicin and topical piroxicam in the treatment of acute trauma-induced pain: A randomized double-blind trial. Am J Emerg Med. 2020;38(9):1767-1771. PubMed
- Lassen CL, Meyer K, Bredthauer A, Klier TW. Facial and oral cross-contamination of a 3-year-old child with high concentration capsaicin: A case report. A A Pract. 2020;14(9):e01258. PubMed
- Predel HG, Ebel-Bitoun C, Peil B, Weiser TW, Lange R. Efficacy and safety of diclofenac?+?capsaicin gel in patients with acute back/neck pain: A multicenter randomized controlled study. Pain Ther. 2020;9(1):279-296. PubMed
- Umigai N, Kozai Y, Saito T, Takara T. Effects of paprika carotenoid supplementation on bone turnover in postmenopausal women: a randomized, double-blind, placebo-controlled, parallel-group comparison study. Food Nutr Res. 2020;64. PubMed
- Trin K, Perino J, Allouchery M, Géniaux H, Miremont G, Salvo F. Second-degree burn induced by high-concentration topical capsaicin with mobility sequelae: A case report. Pain Pract 2023;23(2):216-219. PubMed
Niacin 66 references
- Garg R, Malinow MR, Pettinger M, et al. Niacin treatment increases plasma homocysteine levels. Am Heart J 1999;138:1082-7.
- Anon. Inositol hexaniacinate. Altern Med Rev 1998;3:222-3.
- Knodel LC, Talbert RL. Adverse effects of hypolipidaemic drugs. Med Toxicol 1987;2:10-32. PubMed
- Guyton JR, Blazing MA, Hagar J, et al. Extended-release niacin vs gemfibrozil for the treatment of low levels of high-density lipoprotein cholesterol. Niaspan-Gemfibrozil Study Group. Arch Intern Med 2000;160:1177-84. PubMed
- Gibbons LW, Gonzalez V, Gordon N, Grundy S. The prevalence of side effects with regular and sustained-release nicotinic acid. Am J Med 1995;99:378-85. PubMed
- Whelan AM, Price SO, Fowler SF, Hainer BL. The effect of aspirin on niacin-induced cutaneous reactions. J Fam Pract 1992;34:165-8.
- Jungnickel PW, Maloley PA, Vander Tuin EL, et al. Effect of two aspirin pretreatment regimens on niacin-induced cutaneous reactions. J Gen Intern Med 1997;12:591-6. PubMed
- Capuzzi DM, Guyton JR, Morgan JM, et al. Efficacy and safety of an extended-release niacin (Niaspan): a long-term study. Am J Cardiol 1998;82:74-81;disc. 85U-6U. PubMed
- Gray DR, Morgan T, Chretien SD, Kashyap ML. Efficacy and safety of controlled-release niacin in dyslipoproteinemic veterans. Ann Intern Med 1994;121:252-8. PubMed
- McKenney JM, Proctor JD, Harris S, Chinchili VM. A comparison of the efficacy and toxic effects of sustained- vs immediate-release niacin in hypercholesterolemic patients. JAMA 1994;271:672-7. DOI
- Knopp RH, Alagona P, Davidson M, et al. Equivalent efficacy of a time-release form of niacin (Niaspan) given once-a-night versus plain niacin in the management of hyperlipidemia. Metabolism 1998;47:1097-104. PubMed
- Knopp RH. Clinical profiles of plain versus sustained-release niacin (Niaspan) and the physiologic rationale for nighttime dosing. Am J Cardiol 1998;82:24U-28U;discussion 39U-41U. PubMed
- Garg A, Grundy SM. Nicotinic acid as therapy for dyslipidemia in non-insulin-dependent diabetes mellitus. JAMA 1990;264:723-6. DOI
- Leighton RF, Gordon NF, Small GS, et al. Dental and gingival pain as side effects of niacin therapy. Chest 1998;114:1472-4. PubMed
- American Society of Health-System Pharmacists. ASHP Therapeutic Position Statement on the safe use of niacin in the management of dyslipidemias. Am J Health Syst Pharm 1997;54:2815-9. DOI
- Vega GL, Grundy SM. Lipoprotein responses to treatment with lovastatin, gemfibrozil, and nicotinic acid in normolipidemic patients with hypoalphalipoproteinemia. Arch Intern Med 1994;154:73-82. DOI
- Guyton JR, Goldberg AC, Kreisberg RA, et al. Effectiveness of once-nightly dosing of extended-release niacin alone and in combination for hypercholesterolemia. Am J Cardiol 1998;82:737-43.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Bays HE, Dujovne CA. Drug interactions of lipid-altering drugs. Drug Saf 1998;19:355-71. PubMed
- Rader JI, Calvert RJ, Hathcock JN. Hepatic toxicity of unmodified and time-release preparations of niacin. Am J Med 1992;92:77-81. PubMed
- Kahn SE, Beard JC, Schwartz MW, et al. Increased B-cell secretory capacity as mechanism for islet adaptation to nicotinic acid-induced insulin resistance. Diabetes 1989;38:562-8.
- Schwartz ML. Severe reversible hyperglycemia as a consequence of niacin therapy. Arch Int Med 1993;153:2050-2. DOI
- Raising HDL and Niacin Use. Pharmacist's Letter/Prescriber's Letter 2004;20(5):200504.
- McKenney J. New perspectives on the use of niacin in the treatment of lipid disorders. Arch Intern Med 2004;164:697-705. PubMed
- Reaven P, Witztum JL. Lovastatin, nicotinic acid and rhabdomyolysis (letter). Ann Int Med 1988;109:597-8. PubMed
- Ito MK. Advances in the understanding and management of dyslipidemia: using niacin-based therapies. Am J Health-Syst Pharm 2003;60(suppl 2):s15-21. PubMed
- Schwab RA, Bachhuber BH. Delirium and lactic acidosis caused by ethanol and niacin coingestion. Am J Emerg Med 1991;9:363-5. PubMed
- Product information: Niaspan. Kos Pharmaceuticals. Cranbury, NJ. 2005. Available at www.niaspan.com/professional/content/pdfs/productinfo.pdf. (Accessed 3 March 2006).
- Ding RW, Kolbe K, Merz B, et al. Pharmacokinetics of nicotinic acid-salicylic acid interaction. Clin Pharmacol Ther 1989;46:642-7. PubMed
- NIH News. NIH stops clinical trial on combination cholesterol treatment. May 26, 2011. http://www.nih.gov/news/health/may2011/nhlbi-26.htm. (Accessed 3 June 2011).
- Dearing BD, Lavie CJ, Lohmann TP, Genton E. Niacin-induced clotting factor synthesis deficiency with coagulopathy. Arch Intern Med. 1992;152(4):861-3. DOI
- O'Brien T, Silverberg JD, Nguyen TT. Nicotinic acid-induced toxicity associated with cytopenia and decreased levels of thyroxine-binding globulin. Mayo Clin Proc. 1992;67(5):465-8. PubMed
- Gadegbeku CA, Dhandayuthapani A, Shrayyef MZ, Egan BM. Hemodynamic effects of nicotinic acid infusion in normotensive and hypertensive subjects. Am J Hypertens. 2003;16(1):67-71. PubMed
- Garnett WR. Interactions with hydroxymethylglutaryl-coenzyme A reductase inhibitors. Am J Health Syst Pharm. 1995;52(15):1639-45. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Dunn RT, Ford MA, Rindone JP, Kwiecinski FA. Low-Dose Aspirin and Ibuprofen Reduce the Cutaneous Reactions Following Niacin Administration. Am J Ther. 1995;2(7):478-480. PubMed
- Cashin-Hemphill L, Spencer CA, Nicoloff JT, et al. Alterations in serum thyroid hormonal indices with colestipol-niacin therapy. Ann Intern Med. 1987;107(3):324-9. PubMed
- Drinka PJ. Alterations in thyroid and hepatic function tests associated with preparations of sustained-release niacin. Mayo Clin Proc. 1992;67(12):1206. PubMed
- Shakir KM, Kroll S, Aprill BS, Drake AJ 3rd, Eisold JF. Nicotinic acid decreases serum thyroid hormone levels while maintaining a euthyroid state. Mayo Clin Proc. 1995;70(6):556-8. PubMed
- Etchason JA, Miller TD, Squires RW, et al. Niacin-induced hepatitis: a potential side effect with low-dose time-release niacin. Mayo Clin Proc. 1991;66(1):23-8. PubMed
- Henkin Y, Johnson KC, Segrest JP. Rechallenge with crystalline niacin after drug-induced hepatitis from sustained-release niacin. JAMA. 1990;264(2):241-3. DOI
- Henkin Y, Oberman A, Hurst DC, Segrest JP. Niacin revisited: clinical observations on an important but underutilized drug. Am J Med. 1991;91(3):239-46. PubMed
- Brown BG, Bardsley J, Poulin D, et al. Moderate dose, three-drug therapy with niacin, lovastatin, and colestipol to reduce low-density lipoprotein cholesterol <100 mg/dl in patients with hyperlipidemia and coronary artery disease. Am J Cardiol. 1997;80(2)
- Goldberg A, Alagona P Jr, Capuzzi DM, et al. Multiple-dose efficacy and safety of an extended-release form of niacin in the management of hyperlipidemia. Am J Cardiol. 2000;85(9):1100-5. PubMed
- Aronov DM, Keenan JM, Akhmedzhanov NM, et al. Clinical trial of wax-matrix sustained-release niacin in a Russian population with hypercholesterolemia. Arch Fam Med. 1996;5(10):567-75. PubMed
- Morgan JM, Capuzzi DM, Guyton JR, et al. Treatment Effect of Niaspan, a Controlled-release Niacin, in Patients With Hypercholesterolemia: A Placebo-controlled Trial. J Cardiovasc Pharmacol Ther. 1996;1(3):195-202. PubMed
- Andersson RG, Aberg G, Brattsand R, Ericsson E, Lundholm L. Studies on the mechanism of flush induced by nicotinic acid. Acta Pharmacol Toxicol (Copenh). 1977 Jul;41(1):1-10. PubMed
- Brown WV. Niacin for lipid disorders. Indications, effectiveness, and safety. Postgrad Med. 1995 Aug;98(2):185-9, 192-3. PubMed
- O'REILLY PO, CALLBECK MJ, HOFFER A. Sustained-release nicotinic acid (nicospan); effect on (1) cholesterol levels and (2) leukocytes. Can Med Assoc J. 1959;80(5):359-62.
- Gharavi AG, Diamond JA, Smith DA, Phillips RA. Niacin-induced myopathy. Am J Cardiol. 1994;74(8):841-2. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Fraunfelder FW, Fraunfelder FT, Illingworth DR. Adverse ocular effects associated with niacin therapy. Br J Ophthalmol 1995;79:54-56. PubMed
- Ali EH, McJunkin B, Jubelirer S, Hood W. Niacin induced coagulopathy as a manifestation of occult liver injury. W V Med J. 2013 Jan-Feb;109(1):12-4
- Aramwit P, Srisawadwong R, Supasyndh O. Effectiveness and safety of extended-release nicotinic acid for reducing serum phosphorus in hemodialysis patients. J Nephrol. 2012 May-Jun;25(3):354-62. PubMed
- Bassan M. A case for immediate-release niacin. Heart Lung. 2012 Jan-Feb;41(1):95-8. PubMed
- Davidson MH, Rooney M, Pollock E, Drucker J, Choy Y. Effect of colesevelam and niacin on low-density lipoprotein cholesterol and glycemic control in subjects with dyslipidemia and impaired fasting glucose. J Clin Lipidol. 2013 Sep-Oct;7(5):423-32. PubMed
- Guyton JR, Fazio S, Adewale AJ, Jensen E, Tomassini JE, Shah A, Tershakovec AM. Effect of extended-release niacin on new-onset diabetes among hyperlipidemic patients treated with ezetimibe/simvastatin in a randomized controlled trial. Diabetes Care. 2012 PubMed
- Loebl T, Raskin S. A novel case report: acute manic psychotic episode after treatment with niacin. J Neuropsychiatry Clin Neurosci. 2013 Fall;25(4):E14. PubMed
- Teo KK, Goldstein LB, Chaitman BR, Grant S, Weintraub WS, Anderson DC, Sila CA, Cruz-Flores S, Padley RJ, Kostuk WJ, Boden WE; AIM-HIGH Investigators. Extended-release niacin therapy and risk of ischemic stroke in patients with cardiovascular disease: the
- Goldie C, Taylor AJ, Nguyen P, McCoy C, Zhao XQ, Preiss D. Niacin therapy and the risk of new-onset diabetes: a meta-analysis of randomized controlled trials. Heart. 2016 Feb;102(3):198-203.
- Schandelmaier S, Briel M, Saccilotto R, Olu KK, Arpagaus A, Hemkens LG, Nordmann AJ. Niacin for primary and secondary prevention of cardiovascular events. Cochrane Database Syst Rev. 2017 Jun 14;6:CD009744. PubMed
- Jenkins DJA, Spence JD, Giovannucci EL, et al. Supplemental vitamins and minerals for CVD prevention and treatment. J Am Coll Cardiol 2018;71(22):2570-84. PubMed
- Song S, Lee CJ, Oh J, Park S, Kang SM, Lee SH. Effect of Niacin on Carotid Atherosclerosis in Patients at Low-Density Lipoprotein-Cholesterol Goal but High Lipoprotein (a) Level: a 2-Year Follow-Up Study. J Lipid Atheroscler. 2019;8(1):58-66. PubMed
- Kimura H, Umemori Y, Yuki D. Anaphylactic shock-like symptoms due to niacin overdose: A case report. J Dermatol 2022;49(8):e287-e288. PubMed
- Nawaz N, Mistretta T, Karime C, Lewis J, Wolf E. Cholestatic Drug-Induced Liver Injury in a Patient Taking High-Dose Niacin for Hyperlipidemia. J Investig Med High Impact Case Rep 2024;12:23247096231224349. PubMed
Guarana 114 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Harder S, Fuhr U, Staib AH, Wolff T. Ciprofloxacin-caffeine: a drug interaction established using in vivo and in vitro investigations. Am J Med 1989;87:89S-91S. PubMed
- Carbo M, Segura J, De la Torre R, et al. Effect of quinolones on caffeine disposition. Clin Pharmacol Ther 1989;45:234-40. PubMed
- Healy DP, Polk RE, Kanawati L, et al. Interaction between oral ciprofloxacin and caffeine in normal volunteers. Antimicrob Agents Chemother 1989;33:474-8. PubMed
- Mester R, Toren P, Mizrachi I, et al. Caffeine withdrawal increases lithium blood levels. Biol Psychiatry 1995;37:348-50. PubMed
- Jefferson JW. Lithium tremor and caffeine intake: two cases of drinking less and shaking more. J Clin Psychiatry 1988;49:72-3.
- Joeres R, Klinker H, Heusler H, et al. Influence of mexiletine on caffeine elimination. Pharmacol Ther 1987;33:163-9. PubMed
- Vahedi K, Domingo V, Amarenco P, Bousser MG. Ischemic stroke in a sportsman who consumed MaHuang extract and creatine monohydrate for bodybuilding. J Neurol Neurosurg Psychiatr 2000;68:112-3.
- Wakabayashi K, Kono S, Shinchi K, et al. Habitual coffee consumption and blood pressure: A study of self-defense officials in Japan. Eur J Epidemiol 1998;14:669-73. PubMed
- Hodgson JM, Puddey IB, Burke V, et al. Effects on blood pressure of drinking green and black tea. J Hypertens 1999;17:457-63. PubMed
- Rapuri PB, Gallagher JC, Kinyamu HK, Ryschon KL. Caffeine intake increases the rate of bone loss in elderly women and interacts with vitamin D receptor genotypes. Am J Clin Nutr 2001;74:694-700. PubMed
- The National Toxicology Program (NTP). Caffeine. Center for the Evaluation of Risks to Human Reproduction (CERHR). Available at: http://cerhr.niehs.nih.gov/common/caffeine.html.
- Klebanoff MA, Levine RJ, DerSimonian R, et al. Maternal serum paraxanthine, a caffeine metabolite, and the risk of spontaneous abortion. N Engl J Med 1999;341:1639-44. PubMed
- Eskenazi B. Caffeine—filtering the facts. N Engl J Med 1999;341:1688-9. PubMed
- Fernandes O, Sabharwal M, Smiley T, et al. Moderate to heavy caffeine consumption during pregnancy and relationship to spontaneous abortion and abnormal fetal growth: a meta-analysis. Reprod Toxicol 1998;12:435-44. PubMed
- Pollock BG, Wylie M, Stack JA, et al. Inhibition of caffeine metabolism by estrogen replacement therapy in postmenopausal women. J Clin Pharmacol 1999;39:936-40. PubMed
- Nurminen ML, Niittynen L, Korpela R, Vapaatalo H. Coffee, caffeine and blood pressure: a critical review. Eur J Clin Nutr 1999;53:831-9. PubMed
- Dews PB, Curtis GL, Hanford KJ, O'Brien CP. The frequency of caffeine withdrawal in a population-based survey and in a controlled, blinded pilot experiment. J Clin Pharmacol 1999;39:1221-32. PubMed
- FDA. Proposed rule: dietary supplements containing ephedrine alkaloids. Available at: www.verity.fda.gov (Accessed 25 January 2000).
- Boozer CN, Nasser JA, Heymsfield SB, et al. An herbal supplement containing Ma Huang-Guarana for weight loss: a randomized, double-blind trial. Int J Obes Relat Metab Disord 2001;25:316-24. PubMed
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Hagg S, Spigset O, Mjorndal T, Dahlqvist R. Effect of caffeine on clozapine pharmacokinetics in healthy volunteers. Br J Clin Pharmacol 2000;49:59-63. PubMed
- Tobias JD. Caffeine in the treatment of apnea associated with respiratory syncytial virus infection in neonates and infants. South Med J 2000;93:297-304. DOI
- Watson JM, Jenkins EJ, Hamilton P, et al. Influence of caffeine on the frequency and perception of hypoglycemia in free-living patients with type 1 diabetes. Diabetes Care 2000;23:455-9. PubMed
- Lloyd T, Johnson-Rollings N, Eggli DF, et al. Bone status among postmenopausal women with different habitual caffeine intakes: a longitudinal investigation. J Am Coll Nutr 2000;19:256-61. PubMed
- American Academy of Pediatrics. The transfer of drugs and other chemicals into human milk. Pediatrics 2001;108:776-89. PubMed
- Sinclair CJ, Geiger JD. Caffeine use in sports. A pharmacological review. J Sports Med Phys Fitness 2000;40:71-9.
- Haller CA, Benowitz NL. Adverse cardiovascular and central nervous system events associated with dietary supplements containing ephedra alkaloids. N Engl J Med 2000;343:1833-8. PubMed
- Ali M, Afzal M. A potent inhibitor of thrombin stimulated platelet thromboxane formation from unprocessed tea. Prostaglandins Leukot Med 1987;27:9-13. PubMed
- Ardlie NG, Glew G, Schultz BG, Schwartz CJ. Inhibition and reversal of platelet aggregation by methyl xanthines. Thromb Diath Haemorrh 1967;18:670-3. DOI
- Ferrini RL, Barrett-Connor E. Caffeine intake and endogenous sex steroid levels in postmenopausal women. The Rancho Bernardo Study. Am J Epidemiol 1996:144:642-4. PubMed
- Haller CA, Jacob P 3rd, Benowitz NL. Pharmacology of ephedra alkaloids and caffeine after single-dose dietary supplement use. Clin Pharmacol Ther 2002;71:421-32. PubMed
- Bell DG, Jacobs I, Ellerington K. Effect of caffeine and ephedrine ingestion on anaerobic exercise performance. Med Sci Sports Exerc 2001;33:1399-403. PubMed
- Horner NK, Lampe JW. Potential mechanisms of diet therapy for fibrocystic breast conditions show inadequate evidence of effectiveness. J Am Diet Assoc 2000;100:1368-80. PubMed
- Bracken MB, Triche EW, Belanger K, et al. Association of maternal caffeine consumption with decrements in fetal growth. Am J Epidemiol 2003;157:456-66.. PubMed
- McGowan JD, Altman RE, Kanto WP Jr. Neonatal withdrawal symptoms after chronic maternal ingestion of caffeine. South Med J 1988;81:1092-4.. PubMed
- Nehlig A, Debry G. Consequences on the newborn of chronic maternal consumption of coffee during gestation and lactation: a review. J Am Coll Nutr 1994;13:6-21.. PubMed
- Massey LK. Is caffeine a risk factor for bone loss in the elderly? Am J Clin Nutr 2001;74:569-70. PubMed
- Kockler DR, McCarthy MW, Lawson CL. Seizure activity and unresponsiveness after hydroxycut ingestion. Pharmacotherapy 2001;21:647-51.. PubMed
- Schechter MD, Timmons GD. Objectively measured hyperactivity--II. Caffeine and amphetamine effects. J Clin Pharmacol 1985;25:276-80.. PubMed
- Nix D, Zelenitsky S, Symonds W, et al. The effect of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. Clin Pharmacol Ther 1992;51:183. DOI
- Infante S, Baeza ML, Calvo M, et al. Anaphylaxis due to caffeine. Allergy 2003;58:681-2. PubMed
- Massey LK, Whiting SJ. Caffeine, urinary calcium, calcium metabolism and bone. J Nutr 1993;123:1611-4. PubMed
- Nawrot P, Jordan S, Eastwood J, et al. Effects of caffeine on human health. Food Addit Contam 2003;20:1-30. PubMed
- May DC, Jarboe CH, VanBakel AB, Williams WM. Effects of cimetidine on caffeine disposition in smokers and nonsmokers. Clin Pharmacol Ther 1982;31:656-61. PubMed
- Abernethy DR, Todd EL. Impairment of caffeine clearance by chronic use of low-dose oestrogen-containing oral contraceptives. Eur J Clin Pharmacol 1985;28:425-8. PubMed
- Brown NJ, Ryder D, Branch RA. A pharmacodynamic interaction between caffeine and phenylpropanolamine. Clin Pharmacol Ther 1991;50:363-71. PubMed
- Sanderink GJ, Bournique B, Stevens J, et al. Involvement of human CYP1A isoenzymes in the metabolism and drug interactions of riluzole in vitro. Pharmacol Exp Ther 1997;282:1465-72. DOI
- Wahllander A, Paumgartner G. Effect of ketoconazole and terbinafine on the pharmacokinetics of caffeine in healthy volunteers. Eur J Clin Pharmacol 1989;37:279-83. PubMed
- Carrillo JA, Benitez J. Clinically significant pharmacokinetic interactions between dietary caffeine and medications. Clin Pharmacokinet 2000;39:127-53. PubMed
- Underwood DA. Which medications should be held before a pharmacologic or exercise stress test? Cleve Clin J Med 2002;69:449-50. PubMed
- Aqel RA, Zoghbi GJ, Trimm JR, et al. Effect of caffeine administered intravenously on intracoronary-administered adenosine-induced coronary hemodynamics in patients with coronary artery disease. Am J Cardiol 2004;93:343-6. PubMed
- Zheng XM, Williams RC. Serum caffeine levels after 24-hour abstention: clinical implications on dipyridamole (201)Tl myocardial perfusion imaging. J Nucl Med Technol 2002;30:123-7.
- Institute of Medicine. Caffeine for the Sustainment of Mental Task Performance: Formulations for Military Operations. Washington, DC: National Academy Press, 2001. Available at: http://books.nap.edu/books/0309082587/html/index.html. DOI
- Holmgren P, Norden-Pettersson L, Ahlner J. Caffeine fatalities--four case reports. Forensic Sci Int 2004;139:71-3. PubMed
- Dews PB, O'Brien CP, Bergman J. Caffeine: behavioral effects of withdrawal and related issues. Food Chem Toxicol 2002;40:1257-61. PubMed
- Beach CA, Mays DC, Guiler RC, et al. Inhibition of elimination of caffeine by disulfiram in normal subjects and recovering alcoholics. Clin Pharmacol Ther 1986;39:265-70. PubMed
- Leson CL, McGuigan MA, Bryson SM. Caffeine overdose in an adolescent male. J Toxicol Clin Toxicol 1988;26:407-15. PubMed
- Juliano LM, Griffiths RR. A critical review of caffeine withdrawal: empirical validation of symptoms and signs, incidence, severity, and associated features. Psychopharmacology (Berl) 2004;176:1-29. PubMed
- Winkelmayer WC, Stampfer MJ, Willett WC, Curhan GC. Habitual caffeine intake and the risk of hypertension in women. JAMA 2005;294:2330-5. PubMed
- Raaska K, Raitasuo V, Laitila J, Neuvonen PJ. Effect of caffeine-containing versus decaffeinated coffee on serum clozapine concentrations in hospitalised patients. Basic Clin Pharmacol Toxicol 2004;94:13-8. DOI
- Forrest WH Jr, Bellville JW, Brown BW Jr. The interaction of caffeine with pentobarbital as a nighttime hypnotic. Anesthesiology 1972;36:37-41. PubMed
- Lake CR, Rosenberg DB, Gallant S, et al. Phenylpropanolamine increases plasma caffeine levels. Clin Pharmacol Ther 1990;47:675-85. PubMed
- Weng X, Odouli R, Li DK. Maternal caffeine consumption during pregnancy and the risk of miscarriage: a prospective cohort study. Am J Obstet Gynecol 2008;198:279.e1-8. PubMed
- Savitz DA, Chan RL, Herring AH, et al. Caffeine and miscarriage risk. Epidemiology 2008;19:55-62. PubMed
- Mansi IA, Huang J. Rhabdomyolysis in response to weight-loss herbal medicine. Am J Med Sci 2004;327:356-357. PubMed
- Spinella M. Herbal Medicines and Epilepsy: The Potential for Benefit and Adverse Effects. Epilepsy Behav 2001;2(6):524-532. PubMed
- Shet, M. S., McPhaul, M., Fisher, C. W., Stallings, N. R., and Estabrook, R. W. Metabolism of the antiandrogenic drug (Flutamide) by human CYP1A2. Drug Metab Dispos. 1997;25(11):1298-1303.
- Staib, A. H., Stille, W., Dietlein, G., Shah, P. M., Harder, S., Mieke, S., and Beer, C. Interaction between quinolones and caffeine. Drugs 1987;34 Suppl 1:170-174. PubMed
- Stille, W., Harder, S., Mieke, S., Beer, C., Shah, P. M., Frech, K., and Staib, A. H. Decrease of caffeine elimination in man during co-administration of 4-quinolones. J.Antimicrob.Chemother. 1987;20(5):729-734. PubMed
- Fuhr, U., Strobl, G., Manaut, F., Anders, E. M., Sorgel, F., Lopez-de-Brinas, E., Chu, D. T., Pernet, A. G., Mahr, G., Sanz, F., and . Quinolone antibacterial agents: relationship between structure and in vitro inhibition of the human cytochrome P450 isof
- Kot, M. and Daniel, W. A. Effect of diethyldithiocarbamate (DDC) and ticlopidine on CYP1A2 activity and caffeine metabolism: an in vitro comparative study with human cDNA-expressed CYP1A2 and liver microsomes. Pharmacol Rep. 2009;61(6):1216-1220. PubMed
- Gasior, M., Borowicz, K., Buszewicz, G., Kleinrok, Z., and Czuczwar, S. J. Anticonvulsant activity of phenobarbital and valproate against maximal electroshock in mice during chronic treatment with caffeine and caffeine discontinuation. Epilepsia 1996;37(3 PubMed
- Jankiewicz, K., Chroscinska-Krawczyk, M., Blaszczyk, B., and Czuczwar, S. J. [Caffeine and antiepileptic drugs: experimental and clinical data]. Przegl.Lek. 2007;64(11):965-967.
- Luszczki, J. J., Zuchora, M., Sawicka, K. M., Kozinska, J., and Czuczwar, S. J. Acute exposure to caffeine decreases the anticonvulsant action of ethosuximide, but not that of clonazepam, phenobarbital and valproate against pentetrazole-induced seizures i
- Chroscinska-Krawczyk, M., Jargiello-Baszak, M., Walek, M., Tylus, B., and Czuczwar, S. J. Caffeine and the anticonvulsant potency of antiepileptic drugs: experimental and clinical data. Pharmacol.Rep. 2011;63(1):12-18. PubMed
- Vaz, J., Kulkarni, C., David, J., and Joseph, T. Influence of caffeine on pharmacokinetic profile of sodium valproate and carbamazepine in normal human volunteers. Indian J.Exp.Biol. 1998;36(1):112-114.
- Gasior, M., Swiader, M., Przybylko, M., Borowicz, K., Turski, W. A., Kleinrok, Z., and Czuczwar, S. J. Felbamate demonstrates low propensity for interaction with methylxanthines and Ca2+ channel modulators against experimental seizures in mice. Eur.J Phar PubMed
- Mohiuddin, M., Azam, A. T., Amran, M. S., and Hossain, M. A. In vive effects of gliclazide and metformin on the plasma concentration of caffeine in healthy rats. Pak.J Biol Sci 5-1-2009;12(9):734-737.
- Mays, D. C., Camisa, C., Cheney, P., Pacula, C. M., Nawoot, S., and Gerber, N. Methoxsalen is a potent inhibitor of the metabolism of caffeine in humans. Clin.Pharmacol.Ther. 1987;42(6):621-626. PubMed
- Wojcikowski, J. and Daniel, W. A. Perazine at therapeutic drug concentrations inhibits human cytochrome P450 isoenzyme 1A2 (CYP1A2) and caffeine metabolism--an in vitro study. Pharmacol Rep. 2009;61(5):851-858. PubMed
- Daniel, W. A., Syrek, M., Rylko, Z., and Kot, M. Effects of phenothiazine neuroleptics on the rate of caffeine demethylation and hydroxylation in the rat liver. Pol.J Pharmacol 2001;53(6):615-621.
- Norager, C. B., Jensen, M. B., Weimann, A., and Madsen, M. R. Metabolic effects of caffeine ingestion and physical work in 75-year old citizens. A randomized, double-blind, placebo-controlled, cross-over study. Clin Endocrinol (Oxf) 2006;65(2):223-228. PubMed
- Quirce, G. S., Freire, P., Fernandez, R. M., Davila, I., and Losada, E. Urticaria from caffeine. J.Allergy Clin Immunol. 1991;88(4):680-681. PubMed
- Wrenn, K. D. and Oschner, I. Rhabdomyolysis induced by a caffeine overdose. Ann.Emerg.Med. 1989;18(1):94-97. PubMed
- Pola, J., Subiza, J., Armentia, A., Zapata, C., Hinojosa, M., Losada, E., and Valdivieso, R. Urticaria caused by caffeine. Ann.Allergy 1988;60(3):207-208.
- Caballero, T., Garcia-Ara, C., Pascual, C., Diaz-Pena, J. M., and Ojeda, A. Urticaria induced by caffeine. J.Investig.Allergol.Clin Immunol. 1993;3(3):160-162.
- Smits, P., Temme, L., and Thien, T. The cardiovascular interaction between caffeine and nicotine in humans. Clin Pharmacol Ther 1993;54(2):194-204. PubMed
- MacKenzie, T., Comi, R., Sluss, P., Keisari, R., Manwar, S., Kim, J., Larson, R., and Baron, J. A. Metabolic and hormonal effects of caffeine: randomized, double-blind, placebo-controlled crossover trial. Metabolism 2007;56(12):1694-1698. PubMed
- Moisey, L. L., Robinson, L. E., and Graham, T. E. Consumption of caffeinated coffee and a high carbohydrate meal affects postprandial metabolism of a subsequent oral glucose tolerance test in young, healthy males. Br.J Nutr. 2010;103(6):833-841. PubMed
- Chroscinska-Krawczyk, M., Ratnaraj, N., Patsalos, P. N., and Czuczwar, S. J. Effect of caffeine on the anticonvulsant effects of oxcarbazepine, lamotrigine and tiagabine in a mouse model of generalized tonic-clonic seizures. Pharmacol Rep. 2009;61(5):819 PubMed
- Simmonds, M. J., Minahan, C. L., and Sabapathy, S. Caffeine improves supramaximal cycling but not the rate of anaerobic energy release. Eur.J Appl Physiol 2010;109(2):287-295. PubMed
- Buscemi, S., Verga, S., Batsis, J. A., Donatelli, M., Tranchina, M. R., Belmonte, S., Mattina, A., Re, A., and Cerasola, G. Acute effects of coffee on endothelial function in healthy subjects. Eur.J Clin Nutr. 2010;64(5):483-489. PubMed
- Rigato, I., Blarasin, L., and Kette, F. Severe hypokalemia in 2 young bicycle riders due to massive caffeine intake. Clin J Sport Med. 2010;20(2):128-130. PubMed
- Ernest, D., Chia, M., and Corallo, C. E. Profound hypokalaemia due to Nurofen Plus and Red Bull misuse. Crit Care Resusc. 2010;12(2):109-110. DOI
- Clausen, T. Hormonal and pharmacological modification of plasma potassium homeostasis. Fundam.Clin Pharmacol 2010;24(5):595-605. PubMed
- Orozco-Gregorio, H., Mota-Rojas, D., Bonilla-Jaime, H., Trujillo-Ortega, M. E., Becerril-Herrera, M., Hernandez-Gonzalez, R., and Villanueva-Garcia, D. Effects of administration of caffeine on metabolic variables in neonatal pigs with peripartum asphyxia PubMed
- du, Boisgueheneuc F., Lannuzel, A., Caparros-Lefebvre, D., and De Broucker, T. [Cerebral infarction in a patient consuming MaHuang extract and guarana]. Presse Med 2-3-2001;30(4):166-167.
- Baghkhani, L. and Jafari, M. Cardiovascular adverse reactions associated with Guarana: is there a causal effect? J.Herb.Pharmacother. 2002;2(1):57-61. DOI
- Haller, C. A., Jacob, P., and Benowitz, N. L. Short-term metabolic and hemodynamic effects of ephedra and guarana combinations. Clin.Pharmacol.Ther. 2005;77(6):560-571. PubMed
- Bydlowski, S. P., D'Amico, E. A., and Chamone, D. A. An aqueous extract of guarana (Paullinia cupana) decreases platelet thromboxane synthesis. Braz.J.Med.Biol.Res. 1991;24(4):421-424.
- Bydlowski, S. P., Yunker, R. L., and Subbiah, M. T. A novel property of an aqueous guarana extract (Paullinia cupana): inhibition of platelet aggregation in vitro and in vivo. Braz.J.Med.Biol.Res. 1988;21(3):535-538.
- Galduroz, J. C. and Carlini, E. A. The effects of long-term administration of guarana on the cognition of normal, elderly volunteers. Sao Paulo Med.J. 1996;114(1):1073-1078. PubMed
- Mattei, R., Dias, R. F., Espinola, E. B., Carlini, E. A., and Barros, S. B. Guarana (Paullinia cupana): toxic behavioral effects in laboratory animals and antioxidants activity in vitro. J.Ethnopharmacol. 1998;60(2):111-116.
- Chamone, D. A., Silva, M. I., Cassaro, C., Bellotti, G., Massumoto, C. M., and Fujimura, A. Y. Guaraná (Paullinia cupana) inhibits aggregation in whole blood. Thrombosis and Haemostasis 1987;58(1):474.
- van der Hoeven N, Visser I, Schene A, van den Born BJ. Severe hypertension related to caffeinated coffee and tranylcypromine: a case report. Ann Intern Med. 2014 May 6;160(9):657-8. doi: 10.7326/L14-5009-8. No abstract available. PubMed
- del Giglio AB, Cubero Dde I, Lerner TG, Guariento RT, de Azevedo RG, Paiva H, Goldman C, Carelli B, Cruz FM, Schindler F, Pianowski L, de Matos LL, del Giglio A. Purified dry extract of Paullinia cupana (guaraná) (PC-18) for chemotherapy-related fatigue i
- Palma CG, Lera AT, Lerner T, de Oliveira MM, de Borta TM, Barbosa RP, Brito GM, Guazzelli CA, Cruz FJ, del Giglio A. Guarana (Paullinia cupana) Improves Anorexia in Patients with Advanced Cancer. J Diet Suppl. 2016;13(2):221-31.
- Wikoff D, Welsh BT, Henderson R, et al. Systematic review of the potential adverse effects of caffeine consumption in healthy adults, pregnant women, adolescents, and children. Food Chem Toxicol 2017;109:585-648. PubMed
- de Araujo DP, Pereira PTVT, Fontes AJC, et al. The use of guarana (Paullinia cupana) as a dietary supplement for fatigue in cancer patients: a systematic review with a meta-analysis. Support Care Cancer 2021;29(12):7171-7182. PubMed
- Zheng KH, Zhu K, Wactawski-Wende J, et al. Caffeine intake from coffee and tea and invasive breast cancer incidence among postmenopausal women in the Women's Health Initiative. Int J Cancer 2021;149(12):2032-2044. PubMed
- Wang S, Li X, Yang Y, et al. Does coffee, tea and caffeine consumption reduce the risk of incident breast cancer? A systematic review and network meta-analysis. Public Health Nutr 2021;24(18):6377-6389. PubMed
- Alshabi AM, Alkahtani SA, Shaikh IA, Habeeb MS. Caffeine modulates pharmacokinetic and pharmacodynamic profiles of pioglitazone in diabetic rats: Impact on therapeutics. Saudi Med J 2021;42(2):151-160. PubMed
- Gleason JL, Sundaram R, Mitro SD, et al. Association of maternal caffeine consumption during pregnancy with child growth. JAMA Netw Open. 2022;5(10):e2239609. PubMed
Rhodiola 13 references
- Kim SH, Hyun SH, Choung SY. Antioxidative effects of Cinnamomi cassiae and Rhodiola rosea extracts in liver of diabetic mice. Biofactors 2006;26:209-19.
- Kwon YI, Jang HD, Shetty K. Evaluation of Rhodiola crenulata and Rhodiola rosea for management of type II diabetes and hypertension. Asia Pac J Clin Nutr 2006;15:425-32.
- Bystritsky A, Kerwin L, Feusner JD. A pilot study of Rhodiola rosea (Rhodax) for generalized anxiety disorder (GAD). J Altern Complement Med 2008;14:175-80.
- Shevtsov VA, Zholus BI, Shervarly VI, et al. A randomized trial of two different doses of a SHR-5 Rhodiola rosea extract versus placebo and control of capacity for mental work. Phytomedicine 2003;10:95-105. PubMed
- Apostolidis E, Kwon YI, Shetty K. Potential of cranberry-based herbal synergies for diabetes and hypertension management. Asia Pac J Clin Nutr 2006;15:433-41.
- Hellum BH, Tosse A, Hoybakk K, et al. Potent in vitro inhibition of CYP3A4 and P-glycoprotein by Rhodiola rosea. Planta Med 2010;76:331-8.
- Skopriska-Rozewska E, Wojcik R, Siwicki AK, et al. The effect of Rhodiola quadrifida extracts on cellular immunity in mice and rats. Pol J Vet Sci 2008;11:105-11.
- Mishra KP, Chanda S, Shukla K, Ganju L. Adjuvant effect of aqueous extract of Rhodiola imbricate rhizome on the immune responses to tetanus toxoid and ovalbumin in rats. Immunopharmacol Immunotoxicol 2010;32:141-6.
- Li HX, Sze SC, Tong Y, Ng TB. Production of Th1- and Th2-dependent cytokines induced by the Chinese medicine herb, Rhodiola algida, on human peripheral blood monocytes. J Ethnopharmacol 2009;123:257-66. PubMed
- Mishra KP, Ganju L, Chanda S, et al. Aqueous extract of Rhodiola imbricate rhizome stimulates Toll-like receptor 4, granzyme-B and Th1 cytokines in vitro. Immunobiology 2009;214:27-31.
- Thu OK, Nilsen OG, Hellum B. In vitro inhibition of cytochrome P-450 activities and quantification of constituents in a selection of commercial Rhodiola rosea products. Pharm Bio. 2016 Dec;54(12):3249-3256.
- Thu OK, Spigset O, Nilsen OG, Hellum B. Effect of commercial Rhodiola rosea on CYP enzyme activity in humans. Eur J Clin Pharmacol. 2016 Mar;72(3):295-300. PubMed
- Woron J, Siwek M. Unwanted effects of psychotropic drug interactions with medicinal products and diet supplements containing plant extracts. Psychiatr Pol 2018;52(6):983-96. PubMed
Green Tea 219 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Harder S, Fuhr U, Staib AH, Wolff T. Ciprofloxacin-caffeine: a drug interaction established using in vivo and in vitro investigations. Am J Med 1989;87:89S-91S. PubMed
- Carbo M, Segura J, De la Torre R, et al. Effect of quinolones on caffeine disposition. Clin Pharmacol Ther 1989;45:234-40. PubMed
- Healy DP, Polk RE, Kanawati L, et al. Interaction between oral ciprofloxacin and caffeine in normal volunteers. Antimicrob Agents Chemother 1989;33:474-8. PubMed
- Mester R, Toren P, Mizrachi I, et al. Caffeine withdrawal increases lithium blood levels. Biol Psychiatry 1995;37:348-50. PubMed
- Jefferson JW. Lithium tremor and caffeine intake: two cases of drinking less and shaking more. J Clin Psychiatry 1988;49:72-3.
- Mitscher LA, Mitscher LA, Jung M, Shankel D, et al. Chemoprotection: a review of the potential therapeutic antioxidant properties of green tea (Camellia sinensis) and certain of its constituents. Med Res Rev 1997;17:327-65.
- Joeres R, Klinker H, Heusler H, et al. Influence of mexiletine on caffeine elimination. Pharmacol Ther 1987;33:163-9. PubMed
- Vahedi K, Domingo V, Amarenco P, Bousser MG. Ischemic stroke in a sportsman who consumed MaHuang extract and creatine monohydrate for bodybuilding. J Neurol Neurosurg Psychiatr 2000;68:112-3.
- Wakabayashi K, Kono S, Shinchi K, et al. Habitual coffee consumption and blood pressure: A study of self-defense officials in Japan. Eur J Epidemiol 1998;14:669-73. PubMed
- Hodgson JM, Puddey IB, Burke V, et al. Effects on blood pressure of drinking green and black tea. J Hypertens 1999;17:457-63. PubMed
- Booth SL, Madabushi HT, Davidson KW, et al. Tea and coffee brews are not dietary sources of vitamin K-1 (phylloquinone). J Am Diet Assoc 1995;95:82-3. PubMed
- Lou FQ, Zhang MF, Zhang XG, et al. A study on tea-pigment in prevention of atherosclerosis. Chin Med J (Engl) 1989;102:579-83.
- Graham HN. Green tea composition, consumption, and polyphenol chemistry. Prev Med 1992;21:334-50. PubMed
- Rapuri PB, Gallagher JC, Kinyamu HK, Ryschon KL. Caffeine intake increases the rate of bone loss in elderly women and interacts with vitamin D receptor genotypes. Am J Clin Nutr 2001;74:694-700. PubMed
- The National Toxicology Program (NTP). Caffeine. Center for the Evaluation of Risks to Human Reproduction (CERHR). Available at: http://cerhr.niehs.nih.gov/common/caffeine.html.
- Klebanoff MA, Levine RJ, DerSimonian R, et al. Maternal serum paraxanthine, a caffeine metabolite, and the risk of spontaneous abortion. N Engl J Med 1999;341:1639-44. PubMed
- Eskenazi B. Caffeine—filtering the facts. N Engl J Med 1999;341:1688-9. PubMed
- Fernandes O, Sabharwal M, Smiley T, et al. Moderate to heavy caffeine consumption during pregnancy and relationship to spontaneous abortion and abnormal fetal growth: a meta-analysis. Reprod Toxicol 1998;12:435-44. PubMed
- Pollock BG, Wylie M, Stack JA, et al. Inhibition of caffeine metabolism by estrogen replacement therapy in postmenopausal women. J Clin Pharmacol 1999;39:936-40. PubMed
- Dews PB, Curtis GL, Hanford KJ, O'Brien CP. The frequency of caffeine withdrawal in a population-based survey and in a controlled, blinded pilot experiment. J Clin Pharmacol 1999;39:1221-32. PubMed
- FDA. Proposed rule: dietary supplements containing ephedrine alkaloids. Available at: www.verity.fda.gov (Accessed 25 January 2000).
- Weisburger JH. Tea and health: the underlying mechanisms. Proc Soc Exp Biol Med 1999;220:271-5. PubMed
- Taylor JR, Wilt VM. Probable antagonism of warfarin by green tea. Ann Pharmacother 1999;33:426-8. PubMed
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Hagg S, Spigset O, Mjorndal T, Dahlqvist R. Effect of caffeine on clozapine pharmacokinetics in healthy volunteers. Br J Clin Pharmacol 2000;49:59-63. PubMed
- Watson JM, Jenkins EJ, Hamilton P, et al. Influence of caffeine on the frequency and perception of hypoglycemia in free-living patients with type 1 diabetes. Diabetes Care 2000;23:455-9. PubMed
- Lloyd T, Johnson-Rollings N, Eggli DF, et al. Bone status among postmenopausal women with different habitual caffeine intakes: a longitudinal investigation. J Am Coll Nutr 2000;19:256-61. PubMed
- American Academy of Pediatrics. The transfer of drugs and other chemicals into human milk. Pediatrics 2001;108:776-89. PubMed
- Heck AM, DeWitt BA, Lukes AL. Potential interactions between alternative therapies and warfarin. Am J Health Syst Pharm 2000;57:1221-7. DOI
- Sinclair CJ, Geiger JD. Caffeine use in sports. A pharmacological review. J Sports Med Phys Fitness 2000;40:71-9.
- Haller CA, Benowitz NL. Adverse cardiovascular and central nervous system events associated with dietary supplements containing ephedra alkaloids. N Engl J Med 2000;343:1833-8. PubMed
- Ali M, Afzal M. A potent inhibitor of thrombin stimulated platelet thromboxane formation from unprocessed tea. Prostaglandins Leukot Med 1987;27:9-13. PubMed
- Ardlie NG, Glew G, Schultz BG, Schwartz CJ. Inhibition and reversal of platelet aggregation by methyl xanthines. Thromb Diath Haemorrh 1967;18:670-3. DOI
- Ferrini RL, Barrett-Connor E. Caffeine intake and endogenous sex steroid levels in postmenopausal women. The Rancho Bernardo Study. Am J Epidemiol 1996:144:642-4. PubMed
- Pisters KM, Newman RA, Coldman B, et al. Phase I trial of oral green tea extract in adult patients with solid tumors. J Clin Oncol 2001;19:1830-8. PubMed
- Haller CA, Jacob P 3rd, Benowitz NL. Pharmacology of ephedra alkaloids and caffeine after single-dose dietary supplement use. Clin Pharmacol Ther 2002;71:421-32. PubMed
- Bell DG, Jacobs I, Ellerington K. Effect of caffeine and ephedrine ingestion on anaerobic exercise performance. Med Sci Sports Exerc 2001;33:1399-403. PubMed
- Horner NK, Lampe JW. Potential mechanisms of diet therapy for fibrocystic breast conditions show inadequate evidence of effectiveness. J Am Diet Assoc 2000;100:1368-80. PubMed
- Bracken MB, Triche EW, Belanger K, et al. Association of maternal caffeine consumption with decrements in fetal growth. Am J Epidemiol 2003;157:456-66.. PubMed
- McGowan JD, Altman RE, Kanto WP Jr. Neonatal withdrawal symptoms after chronic maternal ingestion of caffeine. South Med J 1988;81:1092-4.. PubMed
- Nehlig A, Debry G. Consequences on the newborn of chronic maternal consumption of coffee during gestation and lactation: a review. J Am Coll Nutr 1994;13:6-21.. PubMed
- Massey LK. Is caffeine a risk factor for bone loss in the elderly? Am J Clin Nutr 2001;74:569-70. PubMed
- Kockler DR, McCarthy MW, Lawson CL. Seizure activity and unresponsiveness after hydroxycut ingestion. Pharmacotherapy 2001;21:647-51.. PubMed
- Nix D, Zelenitsky S, Symonds W, et al. The effect of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. Clin Pharmacol Ther 1992;51:183. DOI
- Ahn WS, Yoo J, Huh SW, et al. Protective effects of green tea extracts (polyphenon E and EGCG) on human cervical lesions. Eur J Cancer Prev 2003;12:383-90. PubMed
- Infante S, Baeza ML, Calvo M, et al. Anaphylaxis due to caffeine. Allergy 2003;58:681-2. PubMed
- Massey LK, Whiting SJ. Caffeine, urinary calcium, calcium metabolism and bone. J Nutr 1993;123:1611-4. PubMed
- Shirai T, Hayakawa H, Akiyama J, et al. Food allergy to green tea. J Allergy Clin Immunol 2003;112:805-6. PubMed
- Jatoi A, Ellison N, Burch PA, et al. A phase II trial of green tea in the treatment of patients with androgen independent metastatic prostate carcinoma. Cancer 2003;97:1442-6.. PubMed
- Nawrot P, Jordan S, Eastwood J, et al. Effects of caffeine on human health. Food Addit Contam 2003;20:1-30. PubMed
- May DC, Jarboe CH, VanBakel AB, Williams WM. Effects of cimetidine on caffeine disposition in smokers and nonsmokers. Clin Pharmacol Ther 1982;31:656-61. PubMed
- Brown NJ, Ryder D, Branch RA. A pharmacodynamic interaction between caffeine and phenylpropanolamine. Clin Pharmacol Ther 1991;50:363-71. PubMed
- Sanderink GJ, Bournique B, Stevens J, et al. Involvement of human CYP1A isoenzymes in the metabolism and drug interactions of riluzole in vitro. Pharmacol Exp Ther 1997;282:1465-72. DOI
- Wahllander A, Paumgartner G. Effect of ketoconazole and terbinafine on the pharmacokinetics of caffeine in healthy volunteers. Eur J Clin Pharmacol 1989;37:279-83. PubMed
- Carrillo JA, Benitez J. Clinically significant pharmacokinetic interactions between dietary caffeine and medications. Clin Pharmacokinet 2000;39:127-53. PubMed
- Underwood DA. Which medications should be held before a pharmacologic or exercise stress test? Cleve Clin J Med 2002;69:449-50. PubMed
- Aqel RA, Zoghbi GJ, Trimm JR, et al. Effect of caffeine administered intravenously on intracoronary-administered adenosine-induced coronary hemodynamics in patients with coronary artery disease. Am J Cardiol 2004;93:343-6. PubMed
- Zheng XM, Williams RC. Serum caffeine levels after 24-hour abstention: clinical implications on dipyridamole (201)Tl myocardial perfusion imaging. J Nucl Med Technol 2002;30:123-7.
- Institute of Medicine. Caffeine for the Sustainment of Mental Task Performance: Formulations for Military Operations. Washington, DC: National Academy Press, 2001. Available at: http://books.nap.edu/books/0309082587/html/index.html. DOI
- Dews PB, O'Brien CP, Bergman J. Caffeine: behavioral effects of withdrawal and related issues. Food Chem Toxicol 2002;40:1257-61. PubMed
- Beach CA, Mays DC, Guiler RC, et al. Inhibition of elimination of caffeine by disulfiram in normal subjects and recovering alcoholics. Clin Pharmacol Ther 1986;39:265-70. PubMed
- Yang YC, Lu FH, Wu JS, et al. The protective effect of habitual tea consumption on hypertension. Arch Intern Med 2004 26;164:1534-40. PubMed
- Son DJ, Cho MR, Jin YR, et al. Antiplatelet effect of green tea catechins: a possible mechanism through arachidonic acid pathway. Prostaglandins Leukot Essent Fatty Acids 2004;71:25-31. PubMed
- Juliano LM, Griffiths RR. A critical review of caffeine withdrawal: empirical validation of symptoms and signs, incidence, severity, and associated features. Psychopharmacology (Berl) 2004;176:1-29. PubMed
- Winkelmayer WC, Stampfer MJ, Willett WC, Curhan GC. Habitual caffeine intake and the risk of hypertension in women. JAMA 2005;294:2330-5. PubMed
- Raaska K, Raitasuo V, Laitila J, Neuvonen PJ. Effect of caffeine-containing versus decaffeinated coffee on serum clozapine concentrations in hospitalised patients. Basic Clin Pharmacol Toxicol 2004;94:13-8. DOI
- Forrest WH Jr, Bellville JW, Brown BW Jr. The interaction of caffeine with pentobarbital as a nighttime hypnotic. Anesthesiology 1972;36:37-41. PubMed
- Lake CR, Rosenberg DB, Gallant S, et al. Phenylpropanolamine increases plasma caffeine levels. Clin Pharmacol Ther 1990;47:675-85. PubMed
- Bonkovsky HL. Hepatotoxicity associated with supplements containing Chinese green tea (Camellia sinensis). Ann Intern Med 2006;144:68-71.
- Gloro R, Hourmand-Ollivier I, Mosquet B, et al. Fulminant hepatitis during self-medication with hydroalcoholic extract of green tea. Eur J Gastroenterol Hepatol 2005;17:1135-7. PubMed
- Donovan JL, Chavin KD, Devane CL, et al. Green tea (Camellia sinensis) extract does not alter cytochrome P450 3A4 or 2D6 activity in healthy volunteers. Drug Metab Dispos 2004;32:906-8. PubMed
- Chu KO, Wang CC, Chu CY, et al. Pharmacokinetic studies of green tea catechins in maternal plasma and fetuses in rats. J Pharm Sci 2006;95:1372-81. PubMed
- Isbrucker RA, Edwards JA, Wolz E, et al. Safety studies on epigallocatechin gallate (EGCG) preparations. Part 3: teratogenicity and reproductive toxicity studies in rats. Food Chem Toxicol 2006;44:651-61. PubMed
- Navarro-Peran E, Cabezas-Herrera J, Garcia-Canovas F, et al. The antifolate activity of tea catechins. Cancer Res 2005;65:2059-64. PubMed
- Jimenez-Saenz M, Martinez-Sanchez, MDC. Acute hepatitis associated with the use of green tea infusions. J Hepatol 2006;44:616-9. PubMed
- Bradley Pharmaceuticals. Veregen Prescribing Information. October 2006.
- Correa A, Stolley A, Liu Y. Prenatal tea consumption and risks of anencephaly and spina bifida. Ann Epidemiol 2000;10:476-7. PubMed
- Weng X, Odouli R, Li DK. Maternal caffeine consumption during pregnancy and the risk of miscarriage: a prospective cohort study. Am J Obstet Gynecol 2008;198:279.e1-8. PubMed
- Savitz DA, Chan RL, Herring AH, et al. Caffeine and miscarriage risk. Epidemiology 2008;19:55-62. PubMed
- Golden ED, Lam PY, Kardosh A, et al. Green tea polyphenols block the anticancer effects of bortezomib and other boronic acid-based proteasome inhibitors. Blood 2009;113:5927-37. PubMed
- Misaka S, Yatabe J, Muller F, et al. Green Tea Ingestion Greatly Reduces Plasma Concentrations of Nadolol in Healthy Subjects. Clin Pharmacol Ther 2014. [Epub ahead of print]. PubMed
- Roth M, Timmermann BN, Hagenbuch B. Interactions of green tea catechins with organic anion-transporting polypeptides. Drug Metab Dispos 2011;39:920-6. PubMed
- Kato Y, Miyazaki T, Kano T, et al. Involvement of influx and efflux transport systems in gastrointestinal absorption of celiprolol. J Pharm Sci 2009;98:2529-39. PubMed
- Chan, H. T., So, L. T., Li, S. W., Siu, C. W., Lau, C. P., and Tse, H. F. Effect of herbal consumption on time in therapeutic range of warfarin therapy in patients with atrial fibrillation. J.Cardiovasc.Pharmacol. 2011;58(1):87-90. PubMed
- Nishikawa, M., Ariyoshi, N., Kotani, A., Ishii, I., Nakamura, H., Nakasa, H., Ida, M., Nakamura, H., Kimura, N., Kimura, M., Hasegawa, A., Kusu, F., Ohmori, S., Nakazawa, K., and Kitada, M. Effects of continuous ingestion of green tea or grape seed extrac
- Shet, M. S., McPhaul, M., Fisher, C. W., Stallings, N. R., and Estabrook, R. W. Metabolism of the antiandrogenic drug (Flutamide) by human CYP1A2. Drug Metab Dispos. 1997;25(11):1298-1303.
- Staib, A. H., Stille, W., Dietlein, G., Shah, P. M., Harder, S., Mieke, S., and Beer, C. Interaction between quinolones and caffeine. Drugs 1987;34 Suppl 1:170-174. PubMed
- Stille, W., Harder, S., Mieke, S., Beer, C., Shah, P. M., Frech, K., and Staib, A. H. Decrease of caffeine elimination in man during co-administration of 4-quinolones. J.Antimicrob.Chemother. 1987;20(5):729-734. PubMed
- Fuhr, U., Strobl, G., Manaut, F., Anders, E. M., Sorgel, F., Lopez-de-Brinas, E., Chu, D. T., Pernet, A. G., Mahr, G., Sanz, F., and . Quinolone antibacterial agents: relationship between structure and in vitro inhibition of the human cytochrome P450 isof
- Kot, M. and Daniel, W. A. Effect of diethyldithiocarbamate (DDC) and ticlopidine on CYP1A2 activity and caffeine metabolism: an in vitro comparative study with human cDNA-expressed CYP1A2 and liver microsomes. Pharmacol Rep. 2009;61(6):1216-1220. PubMed
- Gasior, M., Borowicz, K., Buszewicz, G., Kleinrok, Z., and Czuczwar, S. J. Anticonvulsant activity of phenobarbital and valproate against maximal electroshock in mice during chronic treatment with caffeine and caffeine discontinuation. Epilepsia 1996;37(3 PubMed
- Jankiewicz, K., Chroscinska-Krawczyk, M., Blaszczyk, B., and Czuczwar, S. J. [Caffeine and antiepileptic drugs: experimental and clinical data]. Przegl.Lek. 2007;64(11):965-967.
- Luszczki, J. J., Zuchora, M., Sawicka, K. M., Kozinska, J., and Czuczwar, S. J. Acute exposure to caffeine decreases the anticonvulsant action of ethosuximide, but not that of clonazepam, phenobarbital and valproate against pentetrazole-induced seizures i
- Chroscinska-Krawczyk, M., Jargiello-Baszak, M., Walek, M., Tylus, B., and Czuczwar, S. J. Caffeine and the anticonvulsant potency of antiepileptic drugs: experimental and clinical data. Pharmacol.Rep. 2011;63(1):12-18. PubMed
- Vaz, J., Kulkarni, C., David, J., and Joseph, T. Influence of caffeine on pharmacokinetic profile of sodium valproate and carbamazepine in normal human volunteers. Indian J.Exp.Biol. 1998;36(1):112-114.
- Gasior, M., Swiader, M., Przybylko, M., Borowicz, K., Turski, W. A., Kleinrok, Z., and Czuczwar, S. J. Felbamate demonstrates low propensity for interaction with methylxanthines and Ca2+ channel modulators against experimental seizures in mice. Eur.J Phar PubMed
- Mohiuddin, M., Azam, A. T., Amran, M. S., and Hossain, M. A. In vive effects of gliclazide and metformin on the plasma concentration of caffeine in healthy rats. Pak.J Biol Sci 5-1-2009;12(9):734-737.
- Mays, D. C., Camisa, C., Cheney, P., Pacula, C. M., Nawoot, S., and Gerber, N. Methoxsalen is a potent inhibitor of the metabolism of caffeine in humans. Clin.Pharmacol.Ther. 1987;42(6):621-626. PubMed
- Wojcikowski, J. and Daniel, W. A. Perazine at therapeutic drug concentrations inhibits human cytochrome P450 isoenzyme 1A2 (CYP1A2) and caffeine metabolism--an in vitro study. Pharmacol Rep. 2009;61(5):851-858. PubMed
- Daniel, W. A., Syrek, M., Rylko, Z., and Kot, M. Effects of phenothiazine neuroleptics on the rate of caffeine demethylation and hydroxylation in the rat liver. Pol.J Pharmacol 2001;53(6):615-621.
- Norager, C. B., Jensen, M. B., Weimann, A., and Madsen, M. R. Metabolic effects of caffeine ingestion and physical work in 75-year old citizens. A randomized, double-blind, placebo-controlled, cross-over study. Clin Endocrinol (Oxf) 2006;65(2):223-228. PubMed
- Wang, X. and Yeung, J. H. Effects of the aqueous extract from Salvia miltiorrhiza Bunge on caffeine pharmacokinetics and liver microsomal CYP1A2 activity in humans and rats. J Pharm Pharmacol 2010;62(8):1077-1083.
- Kot M, Daniel WA. Caffeine as a marker substrate for testing cytochrome P450 activity in human and rat. Pharmacol Rep 2008;60:789-97.
- Kjaerstad MB, Nielsen F, Nohr-Jensen L, et al. Systemic uptake of miconazole during vaginal suppository use and effect on CYP1A2 and CYP3A4 associated enzyme activities in women. Eur J Clin Pharmacol 2010;66:1189-97. PubMed
- Goh BC, Reddy NJ, Dandamudi UB, et al. An evaluation of the drug interaction potential of pazopanib, an oral vascular endothelial growth factor receptor tyrosine kinase inhibitor, using a modified Cooperstown 5+1 cocktail in patients with advanced solid t
- Chen Y, Kang Z, Yan J, et al. Liu wei di huang wan, a well-known traditional Chinese medicine induces CYP1A2 while suppressing CYP2A6 and N-acetyltransferase 2 acivities in man. J Ethnopharmacol 2010;132:213-8.
- Suzuki S, Murayama Y, Sugiyama E, et al. Estimating pediatric doses of drugs metabolized by cytochrome P450 (CYP) isozymes, based on physiological liver development and serum protein levels. Yakugaku Zasshi 2010;130:613-20. PubMed
- Chien CF, Wu YT, Lee WC, et al. Herb-drug interaction of Andrographis paniculata extract and andrographolide on the pharmacokinetics of theophylline in rats. Chem Biol Interact 2010;184:458-65. PubMed
- Mills BM, Zaya MJ, Walters RR, et al. Current cytochrome P450 phenotyping methods applied to metabolic drug -drug interaction prediction in dogs. Drug Metab Dispos 2010;38:396-404. PubMed
- Turpault S, Brian W, Van Horn R, et al. Pharmacokinetic assessment of a five-probe cocktail for CYPs 1A2, 2C9, 2C19, 2D6, and 3A. Br J Clin Pharmacol 2009;68:928-35. PubMed
- Filimonova AA, Ziganshina LE, Ziganshin AU, Chichirov AA. On the possibility of patient phenotyping on the basis of cytochrome p-450 1A2 isoenzyme activity using caffeine as the test substrate. Eksp Klin Farmakol 2009;72:61-5.
- Jenkins J, Williams D, Deng Y, et al. Eltrombopag, an oral thrombopoietin receptor agonist, has no impact on the pharmacokinetic profile of probe drugs for cytochrome P450 isoenzymes CYP3A4, CYP1A2, CYP2C9 and CYP2C19 in healthy men: a cocktail analysis.
- Chow, H. H., Cai, Y., Hakim, I. A., Crowell, J. A., Shahi, F., Brooks, C. A., Dorr, R. T., Hara, Y., and Alberts, D. S. Pharmacokinetics and safety of green tea polyphenols after multiple-dose administration of epigallocatechin gallate and polyphenon E i
- Gross, G., Meyer, K. G., Pres, H., Thielert, C., Tawfik, H., and Mescheder, A. A randomized, double-blind, four-arm parallel-group, placebo-controlled Phase II/III study to investigate the clinical efficacy of two galenic formulations of Polyphenon E in
- Stockfleth, E., Beti, H., Orasan, R., Grigorian, F., Mescheder, A., Tawfik, H., and Thielert, C. Topical Polyphenon E in the treatment of external genital and perianal warts: a randomized controlled trial. Br.J Dermatol. 2008;158(6):1329-1338.
- Smits, P., Temme, L., and Thien, T. The cardiovascular interaction between caffeine and nicotine in humans. Clin Pharmacol Ther 1993;54(2):194-204. PubMed
- MacKenzie, T., Comi, R., Sluss, P., Keisari, R., Manwar, S., Kim, J., Larson, R., and Baron, J. A. Metabolic and hormonal effects of caffeine: randomized, double-blind, placebo-controlled crossover trial. Metabolism 2007;56(12):1694-1698. PubMed
- Lopez-Garcia, E., Rodriguez-Artalejo, F., Rexrode, K. M., Logroscino, G., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of stroke in women. Circulation 3-3-2009;119(8):1116-1123. PubMed
- Zhang, W., Lopez-Garcia, E., Li, T. Y., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of cardiovascular diseases and all-cause mortality among men with type 2 diabetes. Diabetes Care 2009;32(6):1043-1045. PubMed
- Moisey, L. L., Robinson, L. E., and Graham, T. E. Consumption of caffeinated coffee and a high carbohydrate meal affects postprandial metabolism of a subsequent oral glucose tolerance test in young, healthy males. Br.J Nutr. 2010;103(6):833-841. PubMed
- Chroscinska-Krawczyk, M., Ratnaraj, N., Patsalos, P. N., and Czuczwar, S. J. Effect of caffeine on the anticonvulsant effects of oxcarbazepine, lamotrigine and tiagabine in a mouse model of generalized tonic-clonic seizures. Pharmacol Rep. 2009;61(5):819 PubMed
- Simmonds, M. J., Minahan, C. L., and Sabapathy, S. Caffeine improves supramaximal cycling but not the rate of anaerobic energy release. Eur.J Appl Physiol 2010;109(2):287-295. PubMed
- Buscemi, S., Verga, S., Batsis, J. A., Donatelli, M., Tranchina, M. R., Belmonte, S., Mattina, A., Re, A., and Cerasola, G. Acute effects of coffee on endothelial function in healthy subjects. Eur.J Clin Nutr. 2010;64(5):483-489. PubMed
- Rigato, I., Blarasin, L., and Kette, F. Severe hypokalemia in 2 young bicycle riders due to massive caffeine intake. Clin J Sport Med. 2010;20(2):128-130. PubMed
- Ernest, D., Chia, M., and Corallo, C. E. Profound hypokalaemia due to Nurofen Plus and Red Bull misuse. Crit Care Resusc. 2010;12(2):109-110. DOI
- Conen, D., Chiuve, S. E., Everett, B. M., Zhang, S. M., Buring, J. E., and Albert, C. M. Caffeine consumption and incident atrial fibrillation in women. Am J Clin Nutr 2010;92(3):509-514. PubMed
- Reis, J. P., Loria, C. M., Steffen, L. M., Zhou, X., van, Horn L., Siscovick, D. S., Jacobs, D. R., Jr., and Carr, J. J. Coffee, decaffeinated coffee, caffeine, and tea consumption in young adulthood and atherosclerosis later in life: the CARDIA study. A PubMed
- Clausen, T. Hormonal and pharmacological modification of plasma potassium homeostasis. Fundam.Clin Pharmacol 2010;24(5):595-605. PubMed
- Gronroos, N. N. and Alonso, A. Diet and risk of atrial fibrillation - epidemiologic and clinical evidence -. Circ.J 2010;74(10):2029-2038. PubMed
- Perera, V., Gross, A. S., and McLachlan, A. J. Caffeine and paraxanthine HPLC assay for CYP1A2 phenotype assessment using saliva and plasma. Biomed.Chromatogr. 2010;24(10):1136-1144. PubMed
- Orozco-Gregorio, H., Mota-Rojas, D., Bonilla-Jaime, H., Trujillo-Ortega, M. E., Becerril-Herrera, M., Hernandez-Gonzalez, R., and Villanueva-Garcia, D. Effects of administration of caffeine on metabolic variables in neonatal pigs with peripartum asphyxia PubMed
- Izzo, A. A. and Ernst, E. Interactions between herbal medicines and prescribed drugs: an updated systematic review. Drugs 2009;69(13):1777-1798. PubMed
- Laurie, S. A., Miller, V. A., Grant, S. C., Kris, M. G., and Ng, K. K. Phase I study of green tea extract in patients with advanced lung cancer. Cancer Chemother.Pharmacol. 2005;55(1):33-38. PubMed
- Chiu, A. E., Chan, J. L., Kern, D. G., Kohler, S., Rehmus, W. E., and Kimball, A. B. Double-blinded, placebo-controlled trial of green tea extracts in the clinical and histologic appearance of photoaging skin. Dermatol Surg. 2005;31(7 Pt 2):855-860. PubMed
- Javaid, A. and Bonkovsky, H. L. Hepatotoxicity due to extracts of Chinese green tea (Camellia sinensis): a growing concern. J Hepatol 2006;45(2):334-335. PubMed
- Martinez-Sierra, C., Rendon, Unceta P., and Martin, Herrera L. [Acute hepatitis after green tea ingestion]. Med Clin (Barc.) 6-17-2006;127(3):119.
- Molinari, M., Watt, K. D., Kruszyna, T., Nelson, R., Walsh, M., Huang, W. Y., Nashan, B., and Peltekian, K. Acute liver failure induced by green tea extracts: case report and review of the literature. Liver Transpl. 2006;12(12):1892-1895. PubMed
- Chow, H. H., Hakim, I. A., Vining, D. R., Crowell, J. A., Cordova, C. A., Chew, W. M., Xu, M. J., Hsu, C. H., Ranger-Moore, J., and Alberts, D. S. Effects of repeated green tea catechin administration on human cytochrome P450 activity. Cancer Epidemiol.B PubMed
- Federico, A., Tiso, A., and Loguercio, C. A case of hepatotoxicity caused by green tea. Free Radic.Biol Med 8-1-2007;43(3):474. PubMed
- Sarma, D. N., Barrett, M. L., Chavez, M. L., Gardiner, P., Ko, R., Mahady, G. B., Marles, R. J., Pellicore, L. S., Giancaspro, G. I., and Low, Dog T. Safety of green tea extracts : a systematic review by the US Pharmacopeia. Drug Saf 2008;31(6):469-484. PubMed
- Engdal, S. and Nilsen, O. G. In vitro inhibition of CYP3A4 by herbal remedies frequently used by cancer patients. Phytother.Res. 2009;23(7):906-912.
- Bergman, J. and Schjott, J. Hepatitis caused by Lotus-f3? Basic Clin Pharmacol.Toxicol. 2009;104(5):414-416. PubMed
- Kalus, U., Kiesewetter, H., and Radtke, H. Effect of CYSTUS052 and green tea on subjective symptoms in patients with infection of the upper respiratory tract. Phytother.Res. 2010;24(1):96-100.
- Tatti, S., Stockfleth, E., Beutner, K. R., Tawfik, H., Elsasser, U., Weyrauch, P., and Mescheder, A. Polyphenon E: a new treatment for external anogenital warts. Br.J Dermatol. 2010;162(1):176-184.
- Tsao, A. S., Liu, D., Martin, J., Tang, X. M., Lee, J. J., El-Naggar, A. K., Wistuba, I., Culotta, K. S., Mao, L., Gillenwater, A., Sagesaka, Y. M., Hong, W. K., and Papadimitrakopoulou, V. Phase II randomized, placebo-controlled trial of green tea extra
- Liatsos, G. D., Moulakakis, A., Ketikoglou, I., and Klonari, S. Possible green tea-induced thrombotic thrombocytopenic purpura. Am.J Health Syst.Pharm. 4-1-2010;67(7):531-534. PubMed
- Josic, J., Olsson, A. T., Wickeberg, J., Lindstedt, S., and Hlebowicz, J. Does green tea affect postprandial glucose, insulin and satiety in healthy subjects: a randomized controlled trial. Nutr.J. 2010;9:63. PubMed
- Miller, R. J., Jackson, K. G., Dadd, T., Mayes, A. E., Brown, A. L., and Minihane, A. M. The impact of the catechol-O-methyltransferase genotype on the acute responsiveness of vascular reactivity to a green tea extract. Br.J.Nutr. 2011;105(8):1138-1144.
- Rohde, J., Jacobsen, C., and Kromann-Andersen, H. [Toxic hepatitis triggered by green tea]. Ugeskr.Laeger 1-17-2011;173(3):205-206.
- Tzellos, T. G., Sardeli, C., Lallas, A., Papazisis, G., Chourdakis, M., and Kouvelas, D. Efficacy, safety and tolerability of green tea catechins in the treatment of external anogenital warts: a systematic review and meta-analysis. J.Eur.Acad.Dermatol.Ve PubMed
- Otera, H., Tada, K., Sakurai, T., Hashimoto, K., and Ikeda, A. Hypersensitivity pneumonitis associated with inhalation of catechin-rich green tea extracts. Respiration 2011;82(4):388-392. PubMed
- Yellapu, R. K., Mittal, V., Grewal, P., Fiel, M., and Schiano, T. Acute liver failure caused by 'fat burners' and dietary supplements: a case report and literature review. Can.J.Gastroenterol. 2011;25(3):157-160. PubMed
- Karth, A., Holoshitz, N., Kavinsky, C. J., Trohman, R., and McBride, B. F. A case report of atrial fibrillation potentially induced by hydroxycut: a multicomponent dietary weight loss supplement devoid of sympathomimetic amines. J.Pharm.Pract. 2010;23(3) PubMed
- Hsu, C. H., Liao, Y. L., Lin, S. C., Tsai, T. H., Huang, C. J., and Chou, P. Does supplementation with green tea extract improve insulin resistance in obese type 2 diabetics? A randomized, double-blind, and placebo-controlled clinical trial. Altern.Med.R
- Zheng XX, Xu YL, Li SH, et al. Green tea intake lowers fasting serum total and LDL cholesterol in adults: a meta-analysis of 14 randomized controlled trials. Am.J.Clin.Nutr. 2011;94:601-610. PubMed
- Miller, R. J., Jackson, K. G., Dadd, T., Mayes, A. E., Brown, A. L., Lovegrove, J. A., and Minihane, A. M. The impact of the catechol-O-methyltransferase genotype on vascular function and blood pressure after acute green tea ingestion. Mol.Nutr.Food Res.
- Bogdanski, P., Suliburska, J., Szulinska, M., Stepien, M., Pupek-Musialik, D., and Jablecka, A. Green tea extract reduces blood pressure, inflammatory biomarkers, and oxidative stress and improves parameters associated with insulin resistance in obese, h
- Jurgens, T. M., Whelan, A. M., Killian, L., Doucette, S., Kirk, S., and Foy, E. Green tea for weight loss and weight maintenance in overweight or obese adults. Cochrane.Database.Syst.Rev. 2012;12:CD008650. PubMed
- Sakamoto, O., Saita, N., Yamasaki, H., Tamanoi, M., and Ando, M. Pulmonary granulomatosis caused by aspirated green tea. Chest 1994;106(1):308-309. PubMed
- Jiménez-Encarnación E, Ríos G, Muñoz-Mirabal A, Vilá LM. Euforia-induced acute hepatitis in a patient with scleroderma. BMJ Case Rep 2012;2012. PubMed
- Choi JS, Burm JP. Effects of oral epigallocatechin gallate on the pharmacokinetics of nicardipine in rats. Arch Pharm Res. 2009 Dec;32(12):1721-5. PubMed
- Chung JH, Choi DH, Choi JS. Effects of oral epigallocatechin gallate on the oral pharmacokinetics of verapamil in rats. Biopharm Drug Dispos. 2009 Mar;30(2):90-3. PubMed
- Crew KD, Brown P, Greenlee H, Bevers TB, Arun B, Hudis C, McArthur HL, Chang J, Rimawi M, Vornik L, Cornelison TL, Wang A, Hibshoosh H, Ahmed A, Terry MB, Santella RM, Lippman SM, Hershman DL. Phase IB randomized, double-blinded, placebo-controlled, dose
- Dryden GW, Lam A, Beatty K, Qazzaz HH, McClain CJ. A pilot study to evaluate the safety and efficacy of an oral dose of (-)-epigallocatechin-3-gallate-rich polyphenon E in patients with mild to moderate ulcerative colitis. Inflamm Bowel Dis. 2013 Aug;19(9 PubMed
- Gallo E, Maggini V, Berardi M, Pugi A, Notaro R, Talini G, Vannozzi G, Bagnoli S, Forte P, Mugelli A, Annese V, Firenzuoli F, Vannacci A. Is green tea a potential trigger for autoimmune hepatitis? Phytomedicine. 2013 Oct 15;20(13):1186-9. PubMed
- Liu K, Zhou R, Wang B, Chen K, Shi LY, Zhu JD, Mi MT. Effect of green tea on glucose control and insulin sensitivity: a meta-analysis of 17 randomized controlled trials. Am J Clin Nutr. 2013 Aug;98(2):340-8. PubMed
- Onakpoya I, Spencer E, Heneghan C, Thompson M. The effect of green tea on blood pressure and lipid profile: a systematic review and meta-analysis of randomized clinical trials. Nutr Metab Cardiovasc Dis. 2014 Aug;24:823-36. PubMed
- Patel SS, Beer S, Kearney DL, Phillips G, Carter BA. Green tea extract: a potential cause of acute liver failure. World J Gastroenterol. 2013 Aug 21;19(31):5174-7. PubMed
- Pillukat MH, Bester C, Hensel A, Lechtenberg M, Petereit F, Beckebaum S, Müller KM, Schmidt HH. Concentrated green tea extract induces severe acute hepatitis in a 63-year-old woman--a case report with pharmaceutical analysis. J Ethnopharmacol. 2014 Aug 8; PubMed
- Schönthal AH. Adverse effects of concentrated green tea extracts. Mol Nutr Food Res. 2011 Jun;55(6):874-85. PubMed
- Shiraishi M, Haruna M, Matsuzaki M, Ota E, Murayama R, Murashima S. Association between the serum folate levels and tea consumption during pregnancy. Biosci Trends. 2010 Oct;4(5):225-30.
- Jang EH, Choi JY, Park CS, Lee SK, Kim CE, Park HJ, Kang JS, Lee JW, Kang JH. Effects of green tea extract administration on the pharmacokinetics of clozapine in rats. J Pharm Pharmacol. 2005 Mar;57(3):311-6. PubMed
- Trudel D, Labbé DP, Araya-Farias M, Doyen A, Bazinet L, Duchesne T, Plante M, Grégoire J, Renaud MC, Bachvarov D, Têtu B, Bairati I. A two-stage, single-arm, phase II study of EGCG-enriched green tea drink as a maintenance therapy in women with advanced s
- Zheng XX, Xu YL, Li SH, Hui R, Wu YJ, Huang XH. Effects of green tea catechins with or without caffeine on glycemic control in adults: a meta-analysis of randomized controlled trials. Am J Clin Nutr. 2013 Apr;97(4):750-62. PubMed
- Caldeira D, Martins C, Alves LB, Pereira H, Ferreira JJ, Costa J. Caffeine does not increase the risk of atrial fibrillation: a systematic review and meta-analysis of observational studies. Heart. 2013;99(19):1383-9. doi: 10.1136/heartjnl-2013-303950. Re PubMed
- Cheng M, Hu Z, Lu X, Huang J, Gu D. Caffeine intake and atrial fibrillation incidence: dose response meta-analysis of prospective cohort studies. Can J Cardiol. 2014 Apr;30(4):448-54. doi: 10.1016/j.cjca.2013.12.026. Epub 2014 2. Review. PubMed
- van der Hoeven N, Visser I, Schene A, van den Born BJ. Severe hypertension related to caffeinated coffee and tranylcypromine: a case report. Ann Intern Med. 2014 May 6;160(9):657-8. doi: 10.7326/L14-5009-8. No abstract available. PubMed
- Dixit S, Stein PK, Dewland TA, Dukes JW, Vittinghoff E, Heckbert SR, Marcus GM. Consumption of Caffeinated Products and Cardiac Ectopy. J Am Heart Assoc. 2016 26;5(1). pii: e002503. doi: 10.1161/JAHA.115.002503. PubMed
- Health Canada. Health Product Info Watch. October 2016; 5-6. Available at: http://www.hc-sc.gc.ca/dhp-mps/medeff/bulletin/hpiw-ivps_2016-10-eng.php#a15.
- Green Tea Extract-Containing Natural Health Products - Rare Risk of Serious Liver Injury. Recalls & alerts. November 15, 2017. http://healthycanadians.gc.ca/recall-alert-rappel-avis/hc-sc/2017/65100a-eng.php. Accessed November 10, 2017.
- Mazzanti G, Di Sotto A, Vitalone A. Hepatotoxicity of green tea: an update. Arch Toxicol. 2015;89(8):1175-91. PubMed
- Isomura T, Suzuki S, Origasa H, et al. Liver-related safety assessment of green tea extracts in humans: a systematic review of randomized controlled trials. Eur J Clin Nutr. 2016;70(11):1221-1229. PubMed
- Drug Record: Green Tea (Camellia Sinesis). LiverTox: National Institutes of Health, U.S. Department of Health & Human Services, March 2014. https://livertox.nlm.nih.gov//GreenTea.htm. Accessed November 20, 2017.
- Yates AA, Erdman JW Jr, Shao A, Dolan LC, Griffiths JC. Bioactive nutrients - Time for tolerable upper intake levels to address safety. Regul Toxicol Pharmacol. 2017;84:94-101. PubMed
- Younes M, Aggett P, Aguilar F, et al. EFSA Panel on Food Additives and Nutrient Sources added to Food (ANS). Scientific opinion on the safety of green tea catechins. EFSA Journal 2018;16(4):5239. PubMed
- Zuchinali P, Riberio PA, Pimentel M, da Rosa PR, Zimerman LI, Rohde LE. Effect of caffeine on ventricular arrhythmia: a systematic review and meta-analysis of experimental and clinical studies. Europace 2016 Feb;18(2):257-66. PubMed
- Dostal AM, Samavat H, Bedell S, et al. The safety of green tea extract supplementation in postmenopausal women at risk for breast cancer: results of the Minnesota Green Tea Trial. Food Chem Toxicol. 2015 Sep;83:26-35. PubMed
- Shamekhi Z, Amani R, Habibagahi Z, Namjoyan F, Ghadiri A, Saki Malehi A. A Randomized, Double-blind, Placebo-controlled Clinical Trial Examining the Effects of Green Tea Extract on Systemic Lupus Erythematosus Disease Activity and Quality of Life. Phytoth PubMed
- Lagier D, Nee L, Guieu R, et al. Peri-operative oral caffeine does not prevent postoperative atrial fibrillation after heart valve surgery with cardiopulmonary bypass: a randomized controlled clinical trial. Eur J Anaesthesiol. 2018 Apr 26. [Epub ahead of DOI
- Voskoboinik A, Kalman JM, Kistler PM. Caffeine and arrhythmias: time to grind the data. JACC: Clin Electrophysiol. 2018;4(4):425-32. PubMed
- Chong SJ, Howard KA, Knox C. Hypokalaemia and drinking green tea: a literature review and report of 2 cases. BMJ Case Rep. 2016;2016. pii: bcr2016214425. PubMed
- Qiao J, Gu C, Shang W, et al. Effect of green tea on pharmacokinetics of 5-fluorouracil in rats and pharmacodynamics in human cell lines in vitro. Food Chem Toxicol. 2011;49(6):1410-5. PubMed
- Abe O, Ono T, Sato H, et al. Role of (-)-epigallocatechin gallate in the pharmacokinetic interaction between nadolol and green tea in healthy volunteers. Eur J Clin Pharmacol 2018;74(6):775-83. doi: 10.1007/s00228-018-2436-2. PubMed
- Wikoff D, Welsh BT, Henderson R, et al. Systematic review of the potential adverse effects of caffeine consumption in healthy adults, pregnant women, adolescents, and children. Food Chem Toxicol 2017;109:585-648. PubMed
- Nutescu EA, Shapiro NL, Ibrahim S, et al. Warfarin and its interactions with foods, herbs and other dietary supplements. Expert Opin Drug Saf. 2006;5(3):433-51. PubMed
- Abdelkawy KS, Abdelaziz RM, Abdelmageed AM, Donia AM, El-Khodary NM. Effects of green tea extract on atorvastatin pharmacokinetics in healthy volunteers. Eur J Drug Metab Pharmacokinet. 2020;45(3):351-360. PubMed
- Filippini T, Malavolti M, Borrelli F, et al. Green tea (Camellia sinensis) for the prevention of cancer. Cochrane Database Syst Rev. 2020;3(3):CD005004. PubMed
- Huang S, Xu Q, Liu L, et al. Effect of green tea and (-)-epigallocatechin gallate on the pharmacokinetics of rosuvastatin. Curr Drug Metab. 2020. PubMed
- Mahmoodi M, Hosseini R, Kazemi A, Ofori-Asenso R, Mazidi M, Mazloomi SM. Effects of green tea or green tea catechin on liver enzymes in healthy individuals and people with nonalcoholic fatty liver disease: A systematic review and meta-analysis of randomiz
- Misaka S, Abe O, Ono T, et al. Effects of single green tea ingestion on pharmacokinetics of nadolol in healthy volunteers. Br J Clin Pharmacol. 2020. PubMed
- Oketch-Rabah HA, Roe AL, Rider CV, et al. United States Pharmacopeia (USP) comprehensive review of the hepatotoxicity of green tea extracts. Toxicol Rep. 2020;7:386-402. PubMed
- Kim TE, Ha N, Kim Y, et al. Effect of epigallocatechin-3-gallate, major ingredient of green tea, on the pharmacokinetics of rosuvastatin in healthy volunteers. Drug Des Devel Ther. 2017;11:1409-1416. PubMed
- Misaka S, Ono Y, Uchida A, et al. Impact of green tea catechin ingestion on the pharmacokinetics of lisinopril in healthy volunteers. Clin Transl Sci. 2020. PubMed
- Darweesh RS, El-Elimat T, Zayed A, et al. The effect of grape seed and green tea extracts on the pharmacokinetics of imatinib and its main metabolite, N-desmethyl imatinib, in rats. BMC Pharmacol Toxicol. 2020;21(1):77. PubMed
- Sonoda J, Ogata K, Yoshikawa N, Sato K, Ikeda R, Shimodozono Y. Impact of green tea intake on the pharmacokinetics of celiprolol in healthy subjects. Int J Clin Pharmacol Ther. 2020. PubMed
- Kim S, Park TH, Kim WI, Park S, Kim JH, Cho MK. The effects of green tea on acne vulgaris: A systematic review and meta-analysis of randomized clinical trials. Phytother Res. 2021;35(1):374-383. PubMed
- Percevault S, Charpiat B, Lebossé F, Mabrut JY, Vial T, Colom M. Green tea and hepatoxicity: Two case reports. Therapie 2021. PubMed
- Kajita N, Miyama S, Kinoshita K, Yoshida K, Narita M. Green tea-induced anaphylaxis: The first pediatric case report. Allergol Int 2021;70(4):507-508. PubMed
- Zheng KH, Zhu K, Wactawski-Wende J, et al. Caffeine intake from coffee and tea and invasive breast cancer incidence among postmenopausal women in the Women's Health Initiative. Int J Cancer 2021;149(12):2032-2044. PubMed
- Wang S, Li X, Yang Y, et al. Does coffee, tea and caffeine consumption reduce the risk of incident breast cancer? A systematic review and network meta-analysis. Public Health Nutr 2021;24(18):6377-6389. PubMed
- Alshabi AM, Alkahtani SA, Shaikh IA, Habeeb MS. Caffeine modulates pharmacokinetic and pharmacodynamic profiles of pioglitazone in diabetic rats: Impact on therapeutics. Saudi Med J 2021;42(2):151-160. PubMed
- Gleason JL, Sundaram R, Mitro SD, et al. Association of maternal caffeine consumption during pregnancy with child growth. JAMA Netw Open. 2022;5(10):e2239609. PubMed
- Seufferlein T, Ettrich TJ, Menzler S, et al. Green tea extract to prevent colorectal adenomas, results of a randomized, placebo-controlled clinical trial. Am J Gastroenterol 2022;117(6):884-894. PubMed
- Teramoto M, Yamagishi K, Muraki I, Tamakoshi A, Iso H. Coffee and green tea consumption and cardiovascular disease mortality among people with and without hypertension. J Am Heart Assoc 2023;12(2):e026477. PubMed
- Veerman GDM, van der Werff SC, Koolen SLW, et al. The influence of green tea extract on nintedanib's bioavailability in patients with pulmonary fibrosis. Biomed Pharmacother 2022;151:113101. PubMed
- Misaka S, Ono Y, Taudte RV, et al. Exposure of fexofenadine, but not pseudoephedrine, is markedly decreased by green tea extract in healthy volunteers. Clin Pharmacol Ther 2022;112(3):627-634. PubMed
- Zhao H, Zhu W, Zhao X, et al. Efficacy of epigallocatechin-3-gallate in preventing dermatitis in patients with breast cancer receiving postoperative radiotherapy: A double-blind, placebo-controlled, phase 2 randomized clinical trial. JAMA Dermatol 2022;15 PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
Theacrine 1 reference
- Xu JK, Kurihara H, Zhao L, Yao XS. Theacrine, a special purine alkaloid with sedative and hypnotic properties from Cammelia assamica var. kucha in mice. J Asian Nat Prod Res 2007;9(6-8):665-72.
Octopamine 6 references
- Visentin V, Morin N, Fontana E, et al. Dual action of octopamine on glucose transport into adipocytes: inhibition via beta3-adrenoceptor activation and stimulation via oxidation by amine oxidases. J Pharmacol Exp Ther 2001;299:96-104.
- Health Canada. Synephrine, Octopamine and Caffeine Health Risk Assessment (HRA) Report. Approved May 16, 2011. Accessed November 6, 2019. Available at: http://www.nutratechinc.com/advz/Studies2011/Safety/S1%20Health%20Canada%200511.pdf.
- Pawar RS, Grundel E. Overview of regulation of dietary supplements in the USA and issues of adulteration with phenethylamines (PEAs). Drug Test Anal 2017;9:500-517. PubMed
- Beaumont RE, Cordery P, James LJ, Watson P. Supplementation with a low-dose of octopamine does not influence endurance cycling performance in recreationally active men. J Sci Med Sport. 2017;20(10):952-956. PubMed
- Smedema JP, Müller GJ. Coronary spasm and thrombosis in a bodybuilder using a nutritional supplement containing synephrine, octopamine, tyramine and caffeine. S Afr Med J. 2008;98(5):372-3.
- Fontana E, Morin N, Prévot D, Carpéné C. Effects of octopamine on lipolysis, glucose transport and amine oxidation in mammalian fat cells. Comp Biochem Physiol C Toxicol Pharmacol. 2000;125(1):33-44. PubMed
Diiodothyronine 3 references
Jiaogulan 8 references
- The Review of Natural Products by Facts and Comparisons. St. Louis, MO: Wolters Kluwer Co., 1999.
- Tan H, Liu ZL, Liu MJ. [Antithrombotic effect of Gynostemma pentaphyllum]. Zhingguo Zhong Xi Yi Jie He Za Zhi 1993;13:278-80.
- Chan LY, Chiu PY, Lau TK. An in-vitro study of ginsenoside Rb(1)-induced teratogenicity using a whole rat embryo culture model. Hum Reprod 2003;18:2166-8..
- Huyen VT, Phan DV, Thang P, Hoa NK, Ostenson CG. Gynostemma pentaphyllum Tea Improves Insulin Sensitivity in Type 2 Diabetic Patients. J Nutr Metab. 2013;2013:765383. doi: 10.1155/2013/765383.
- Li Y, Lin W, Huang J, Xie Y, Ma W. Anti-cancer effects of Gynostemma pentaphyllum (Thunb.) Makino (Jiaogulan). Chin Med. 2016 Sep 27;11:43. Review. PubMed
- Huyen VT, Phan DV, Thang P, Ky PT, Hoa NK, Ostenson CG. Antidiabetic effect of add-on Gynostemma pentaphyllum extract therapy with sulfonylureas in type 2 diabetic patients. Evid Based Complement Alternat Med 2012; 452313.
- Huyen VT, Phan DV, Thang P, Hoa NK, Ostenson CG. Antidiabetic effect of Gynostemma pentaphyllum tea in randomly assigned type 2 diabetic patients. Horm Metab Res. 2010;42(5):353-7.
- Rao A, Clayton P, Briskey D. The effect of an orally-dosed Gynostemma pentaphyllum extract (ActivAMP®) on body composition in overweight, adult men and women: a double-blind, randomised, placebo-controlled study. J Hum Nutr Diet 2021.
Black Pepper 29 references
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
- Bano G, Amla V, Raina RK, et al. The effect of piperine on pharmacokinetics of phenytoin in healthy volunteers. Planta Med 1987;53:568-9. PubMed
- Bano G, et al. Effect of piperine on bioavailability and pharmacokinetics of propranolol and theophylline in healthy volunteers. Eur J Clin Pharmacol 1991;41;615-7. PubMed
- Cohle SD, Trestrail JD III, Graham MA, et al. Fatal pepper aspiration. Am J Dis Child 1988;142:633-6. PubMed
- Bhardwaj RK, Glaeser H, Becquemont L, et al. Piperine, a major constituent of black pepper, inhibits human P-glycoprotein and CYP3A4. J Pharmacol Exp Ther 2002;302:645-50. PubMed
- Velpandian T, Jasuja R, Bhardwaj RK, et al. Piperine in food: interference in the pharmacokinetics of phenytoin. Eur J Drug Metab Pharmacokinet 2001;26:241-7. PubMed
- Pattanaik S, Hota D, Prabhakar S, et al. Pharmacokinetic interaction of a single dose of piperine with steady-state carbamazepine in epilepsy patients. Phytother Res 2009;23:1281-6.
- Munakata, M., Kobayashi, K., Niisato-Nezu, J., Tanaka, S., Kakisaka, Y., Ebihara, T., Ebihara, S., Haginoya, K., Tsuchiya, S., and Onuma, A. Olfactory stimulation using black pepper oil facilitates oral feeding in pediatric patients receiving long-term en
- Myers, B. M., Smith, J. L., and Graham, D. Y. Effect of red pepper and black pepper on the stomach. Am J Gastroenterol 1987;82(3):211-214.
- Raghavendra, R. H. and Naidu, K. A. Spice active principles as the inhibitors of human platelet aggregation and thromboxane biosynthesis. Prostaglandins Leukot.Essent.Fatty Acids 2009;81(1):73-78. PubMed
- Subehan, Usia, T., Kadota, S., and Tezuka, Y. Mechanism-based inhibition of human liver microsomal cytochrome P450 2D6 (CYP2D6) by alkamides of Piper nigrum. Planta Med 2006;72(6):527-532.
- Kasibhatta, R. and Naidu, M. U. Influence of piperine on the pharmacokinetics of nevirapine under fasting conditions: a randomised, crossover, placebo-controlled study. Drugs R.D. 2007;8(6):383-391. PubMed
- Usia, T., Iwata, H., Hiratsuka, A., Watabe, T., Kadota, S., and Tezuka, Y. CYP3A4 and CYP2D6 inhibitory activities of Indonesian medicinal plants. Phytomedicine. 2006;13(1-2):67-73. PubMed
- Mujumdar, A. M., Dhuley, J. N., Deshmukh, V. K., Raman, P. H., Thorat, S. L., and Naik, S. R. Effect of piperine on pentobarbitone induced hypnosis in rats. Indian J Exp.Biol. 1990;28(5):486-487.
- Panda, S. and Kar, A. Piperine lowers the serum concentrations of thyroid hormones, glucose and hepatic 5'D activity in adult male mice. Horm.Metab Res. 2003;35(9):523-526. PubMed
- Lawless, H. and Stevens, D. A. Effects of oral chemical irritation on taste. Physiol Behav. 1984;32(6):995-998. PubMed
- Hiwale, A. R., Dhuley, J. N., and Naik, S. R. Effect of co-administration of piperine on pharmacokinetics of beta-lactam antibiotics in rats. Indian J Exp.Biol. 2002;40(3):277-281.
- Han, Y., Chin Tan, T. M., and Lim, L. Y. In vitro and in vivo evaluation of the effects of piperine on P-gp function and expression. Toxicol.Appl.Pharmacol. 8-1-2008;230(3):283-289. PubMed
- Sharma, P., Varma, M. V., Chawla, H. P., and Panchagnula, R. In situ and in vivo efficacy of peroral absorption enhancers in rats and correlation to in vitro mechanistic studies. Farmaco 2005;60(11-12):874-883. PubMed
- Aher, S., Biradar, S., Gopu, C. L., and Paradkar, A. Novel pepper extract for enhanced P-glycoprotein inhibition. J Pharm.Pharmacol. 2009;61(9):1179-1186. PubMed
- Zutshi, R. K., Singh, R., Zutshi, U., Johri, R. K., and Atal, C. K. Influence of piperine on rifampicin blood levels in patients of pulmonary tuberculosis. J Assoc.Physicians India 1985;33(3):223-224.
- Marotta, R. B. and Floch, M. H. Diet and nutrition in ulcer disease. Med Clin North Am 1991;75(4):967-979. PubMed
- Subehan, Usia, T., Iwata, H., Kadota, S., and Tezuka, Y. Mechanism-based inhibition of CYP3A4 and CYP2D6 by Indonesian medicinal plants. J Ethnopharmacol. 5-24-2006;105(3):449-455. PubMed
- Gimenez L, Zacharisen M. Severe pepper allergy in a young child. WMJ. 2011 Jun;110(3):138-9.
- Ren T, Yang M, Xiao M, Zhu J, Xie W, Zuo Z. Time-dependent inhibition of carbamazepine metabolism by piperine in anti-epileptic treatment. Life Sci. 2019;218:314-323. PubMed
- Thomas AB, Choudhary DC, Raje A, Nagrik SS. Pharmacokinetics and pharmacodynamic herb-drug interaction of piperine with atorvastatin in rats. J Chromatogr Sci 2021;59(4):371-80. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Lin F, Hu Y, Zhang Y, Zhao L, Zhong D, Liu J. Predicting Food-Drug Interactions between Piperine and CYP3A4 Substrate Drugs Using PBPK Modeling. Int J Mol Sci 2024;25(20):10955. PubMed
Vitamin E 64 references
- Kim JM, White RH. Effect of vitamin E on the anticoagulant response to warfarin. Am J Cardiol 1996;77:545-6. PubMed
- Corrigan JJ Jr. The effect of vitamin E on warfarin-induced vitamin K deficiency. Ann N Y Acad Sci 1982;393:361-8. PubMed
- Corrigan JJ Jr. Coagulation problems relating to vitamin E. Am J Pediatr Hematol Oncol 1979;1:169-73.
- Corrigan JJ Jr, Marcus FI. Coagulopathy associated with vitamin E ingestion. JAMA 1974;230:1300-1. DOI
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Chang T, Benet LZ, Hebert MF. The effect of water-soluble vitamin E on cyclosporine pharmacokinetics in healthy volunteers. Clin Pharmacol Ther 1996;59:297-303. PubMed
- Pan SH, Lopez RR Jr, Sher LS, et al. Enhanced oral cyclosporine absorption with water-soluble vitamin E early after liver transplantation. Pharmacother 1996;16:59-65. DOI
- Anon. Dietary supplementation with n-3 polyunsaturated fatty acids and vitamin E after myocardial infarction: results of the GISSI-Prevenzione trial. Gruppo Italiano per lo Studio della Soprawivenza nell'Infarto miocardico. Lancet 1999;354:447-55. DOI
- Chappell LC, Seed PT, Briley AL, et al. Effect of antioxidants on the occurrence of pre-eclampsia in women at increased risk: a randomised trial. Lancet 1999;354:810-6. DOI
- Yusuf S, Dagenais G, Pogue J, et al. Vitamin E supplementation and cardiovascular events in high-risk patients. The heart outcomes prevention evaluation study investigators. N Engl J Med 2000;342:154-60. PubMed
- Stephens NG, Parsons A, Schofield PM, et al. Randomised controlled trial of vitamin E in patients with coronary disease: Cambridge Heart Antioxidant Study. Lancet 1996;347:781-6.
- The Alpha-Tocopherol, Beta Carotene Cancer Prevention Study Group. The effect of vitamin E and beta carotene on the incidence of lung cancer and other cancers in male smokers. N Engl J Med 1994;330:1029-35. PubMed
- Takahashi O. Haemorrhagic toxicity of a large dose of alpha-, beta-, gamma- and delta-tocopherols, ubiquinone, beta-carotene, retinol acetate and L-ascorbic acid in the rat. Food Chem Toxicol 1995;33:121-8.
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Sano M, Ernesto C, Thomas RG, et al. A controlled trial of selegiline, alpha-tocopherol, or both as treatment for Alzheimer's disease. The Alzheimer's Disease Cooperative Study. N Engl J Med 1997;336:1216-22. PubMed
- Liede KE, Haukka JK, Saxen LM, Heinonen OP. Increased tendency towards gingival bleeding caused by joint effect of alpha-tocopherol supplementation and acetylsalicylic acid. Ann Med 1998;30:542-6.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Liu M, Wallmon A, Olsson-Mortlock C, et al. Mixed tocopherols inhibit platelet aggregation in humans: potential mechanisms. Am J Clin Nutr 2003;77:700-6. PubMed
- Sokol RJ, Johnson KE, Karrer FM, et al. Improvement of cyclosporin absorption in children after liver transplantation by means of water-soluble vitamin E. Lancet 1991;338:212-4.. PubMed
- Stein JH, Carlsson CM, Papcke-Benson K, et al. The effects of lipid-lowering and antioxidant vitamin therapies on flow-mediated vasodilation of the brachial artery in older adults with hypercholesterolemia. J Am Coll Cardiol 2001;38:1806-13.. PubMed
- Carlsson CM, Papcke-Benson K, Carnes M, et al. Health-related quality of life and long-term therapy with pravastatin and tocopherol (vitamin E) in older adults. Drugs Aging 2002;19:793-805. . PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Schrogie JJ. Coagulopathy and fat-soluble vitamins (letter). JAMA 1975;232:19. DOI
- Celestini A, Pulcinelli FM, Pignatelli P, et al. Vitamin E potentiates the antiplatelet activity of aspirin in collagen-stimulated platelets. Haematologica 2002;87:420-6.
- Stampfer MJ, Jakubowski JA, Faigel D, et al. Vitamin E supplementation effect on human platelet function, arachidonic acid metabolism, and plasma prostacyclin levels. Am J Clin Nutr 1988;47:700-6. PubMed
- Jandak J, Steiner M, Richardson PD. Alpha-tocopherol, an effective inhibitor of platelet adhesion. Blood 1989;73:141-9. DOI
- Freedman JE, Farhat JH, Loscalzo J, Keaney JF. Alpha-tocopherol inhibits aggregation of human platelets by a protein kinase C-dependent mechanism. Circulation 1996;94:2434-40. PubMed
- Steiner M. Vitamin E, a modifier of platelet function: rationale and use in cardiovascular and cerebrovascular disease. Nutr Rev 1999;57:306-9. PubMed
- Brodkin RH, Bleiberg J. Sensitivity to topically applied vitamin E. Arch Dermatol 1965;92:76-7. DOI
- Booth SL, Golly I, Sacheck JM, et al. Effect of vitamin E supplementation on vitamin K status in adults with normal coagulation status. Am J Clin Nutr 2004;80:143-8. PubMed
- Miller ER 3rd, Pastor-Barriuso R, Dalal D, et al. Meta-analysis: High-dosage vitamin E supplementation may increase all-cause mortality. Ann Intern Med 2005;142:60520-53. PubMed
- Lonn E, Bosch J, Yusuf S, et al. HOPE and HOPE-TOO Trial Investigators. Effects of long-term vitamin E supplementation on cardiovascular events and cancer: a randomized controlled trial. JAMA 2005;293:1338-47. PubMed
- Landes N, Pfluger P, Kluth D, et al. Vitamin E activates gene expression via the pregnane X receptor. Biochem Pharmacol 2003;65:269-73. . PubMed
- Brigelius-Flohe R. Vitamin E and drug metabolism. Biochem Biophys Res Commun 2003;305:737-40. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Schurks M, Glynn RJ, Rist PM, et al. Effects of vitamin E on stroke subtypes: meta-analysis of randomized controlled trials. BMJ 2010;341: c5702. doi: 10.1136/bmj.c5702.
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Gaziano JM, Glynn RJ, Christen WG, et al. Vitamins E and C in the prevention of prostate total cancer in men: the physicians' health study II randomised controlled trial. JAMA 2009;301:52-62.
- Hayden KM, Welsh-Bohmer KA, Wengreen HJ, et al; Cache County Investigators. Risk of mortality with vitamin E supplements: the Cache County study. Am L Med 2007;120:180-4. PubMed
- Smedts HP, de Vries JH, Rakhshandehroo M, et al. High maternal vitamin E intake by diet or supplements is associated with congenital heart defects in the offspring. BJOG 2009;116:416-23. PubMed
- Klein EA, Thompson IM Jr, Tangen CM, et al. Vitamin E and the risk of prostate cancer: the Selenium and Vitamin E Cancer Prevention Trial (SELECT). JAMA 2011;306:1549-56. PubMed
- Huang, H. Y., Caballero, B., Chang, S., Alberg, A. J., Semba, R. D., Schneyer, C. R., Wilson, R. F., Cheng, T. Y., Vassy, J., Prokopowicz, G., Barnes, G. J., and Bass, E. B. The efficacy and safety of multivitamin and mineral supplement use to prevent ca
- Sesso, H. D., Buring, J. E., Christen, W. G., Kurth, T., Belanger, C., MacFadyen, J., Bubes, V., Manson, J. E., Glynn, R. J., and Gaziano, J. M. Vitamins E and C in the prevention of cardiovascular disease in men: the Physicians' Health Study II randomiz
- Papaioannou, D., Cooper, K. L., Carroll, C., Hind, D., Squires, H., Tappenden, P., and Logan, R. F. Antioxidants in the chemoprevention of colorectal cancer and colorectal adenomas in the general population: a systematic review and meta-analysis. Colorec PubMed
- Cooper, K., Squires, H., Carroll, C., Papaioannou, D., Booth, A., Logan, R. F., Maguire, C., Hind, D., and Tappenden, P. Chemoprevention of colorectal cancer: systematic review and economic evaluation. Health Technol.Assess. 2010;14(32):1-206. PubMed
- Mathew, M. C., Ervin, A. M., Tao, J., and Davis, R. M. Antioxidant vitamin supplementation for preventing and slowing the progression of age-related cataract. Cochrane.Database.Syst.Rev. 2012;6:CD004567. PubMed
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Soares, K. V. and McGrath, J. J. Vitamin E for neuroleptic-induced tardive dyskinesia. Cochrane.Database.Syst.Rev. 2001;(4):CD000209. DOI
- Roed-Petersen, J. and Hjorth, N. Contact dermatitis from antioxidants. Br.J.Dermatol. 1976;94(3):233-241. PubMed
- Brion, L. P., Bell, E. F., Raghuveer, T. S., and Soghier, L. What is the appropriate intravenous dose of vitamin E for very-low-birth-weight infants? J.Perinatol. 2004;24(4):205-207. PubMed
- Manny, T., Pettus, J., Hemal, A., Marks, M., and Mirzazadeh, M. Penile sclerosing lipogranulomas and disfigurement from use of "1Super Extenze" among Laotian immigrants. J.Sex Med. 2011;8(12):3505-3510. PubMed
- Musso, G., Cassader, M., Rosina, F., and Gambino, R. Impact of current treatments on liver disease, glucose metabolism and cardiovascular risk in non-alcoholic fatty liver disease (NAFLD): a systematic review and meta-analysis of randomised trials. Diabe PubMed
- Bell, E. F. Upper limit of vitamin E in infant formulas. J.Nutr. 1989;119(12 Suppl):1829-1831. PubMed
- Manzano, D., Aguirre, A., Gardeazabal, J., Eizaguirre, X., and Diaz Perez, J. L. Allergic contact dermatitis from tocopheryl acetate (vitamin E) and retinol palmitate (vitamin A) in a moisturizing cream. Contact Dermatitis 1994;31(5):324.
- Barak, Y., Swartz, M., Shamir, E., Stein, D., and Weizman, A. Vitamin E (alpha-tocopherol) in the treatment of tardive dyskinesia: a statistical meta-analysis. Ann.Clin.Psychiatry 1998;10(3):101-105.
- Chae CU, Albert CM, Moorthy MV, et al. Vitamin E supplementation and the risk of heart failure in women. Circ Heart Fail. 2012;5(2):176-82. PubMed
- Rumbold A, Ota E, Hori H, Miyazaki C, Crowther CA. Vitamin E supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004069. PubMed
- Prescribing information: KOSELUGO (selumetinib) capsules. U.S. Food and Drug Administration. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2020/213756s000lbl.pdf.
- Warshaw EM, Ruggiero JL, DeKoven JG, et al. Patch testing with tocopherol and tocopherol acetate: the North American Contact Dermatitis Group experience, 2001 to 2016. Dermatitis. 2021;32(5):308-18. PubMed
- US Preventive Services Task Force, Mangione CM, Barry MJ, et al. Vitamin, Mineral, and Multivitamin Supplementation to Prevent Cardiovascular Disease and Cancer: US Preventive Services Task Force Recommendation Statement. JAMA 2022;327(23):2326-2333. PubMed
- Abrol R, Kaushik R, Goel D, Sama S, Kaushik RM, Kala M. Vitamin E-induced coagulopathy in a young patient: a case report. J Med Case Rep 2023;17(1):107. PubMed
- Abtahi-Naeini B, Rastegarnasab F, Saffaei A. Liquid vitamin E injection for cosmetic facial rejuvenation: A disaster report of lipogranuloma. J Cosmet Dermatol 2022;21(11):5549-5554. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC